


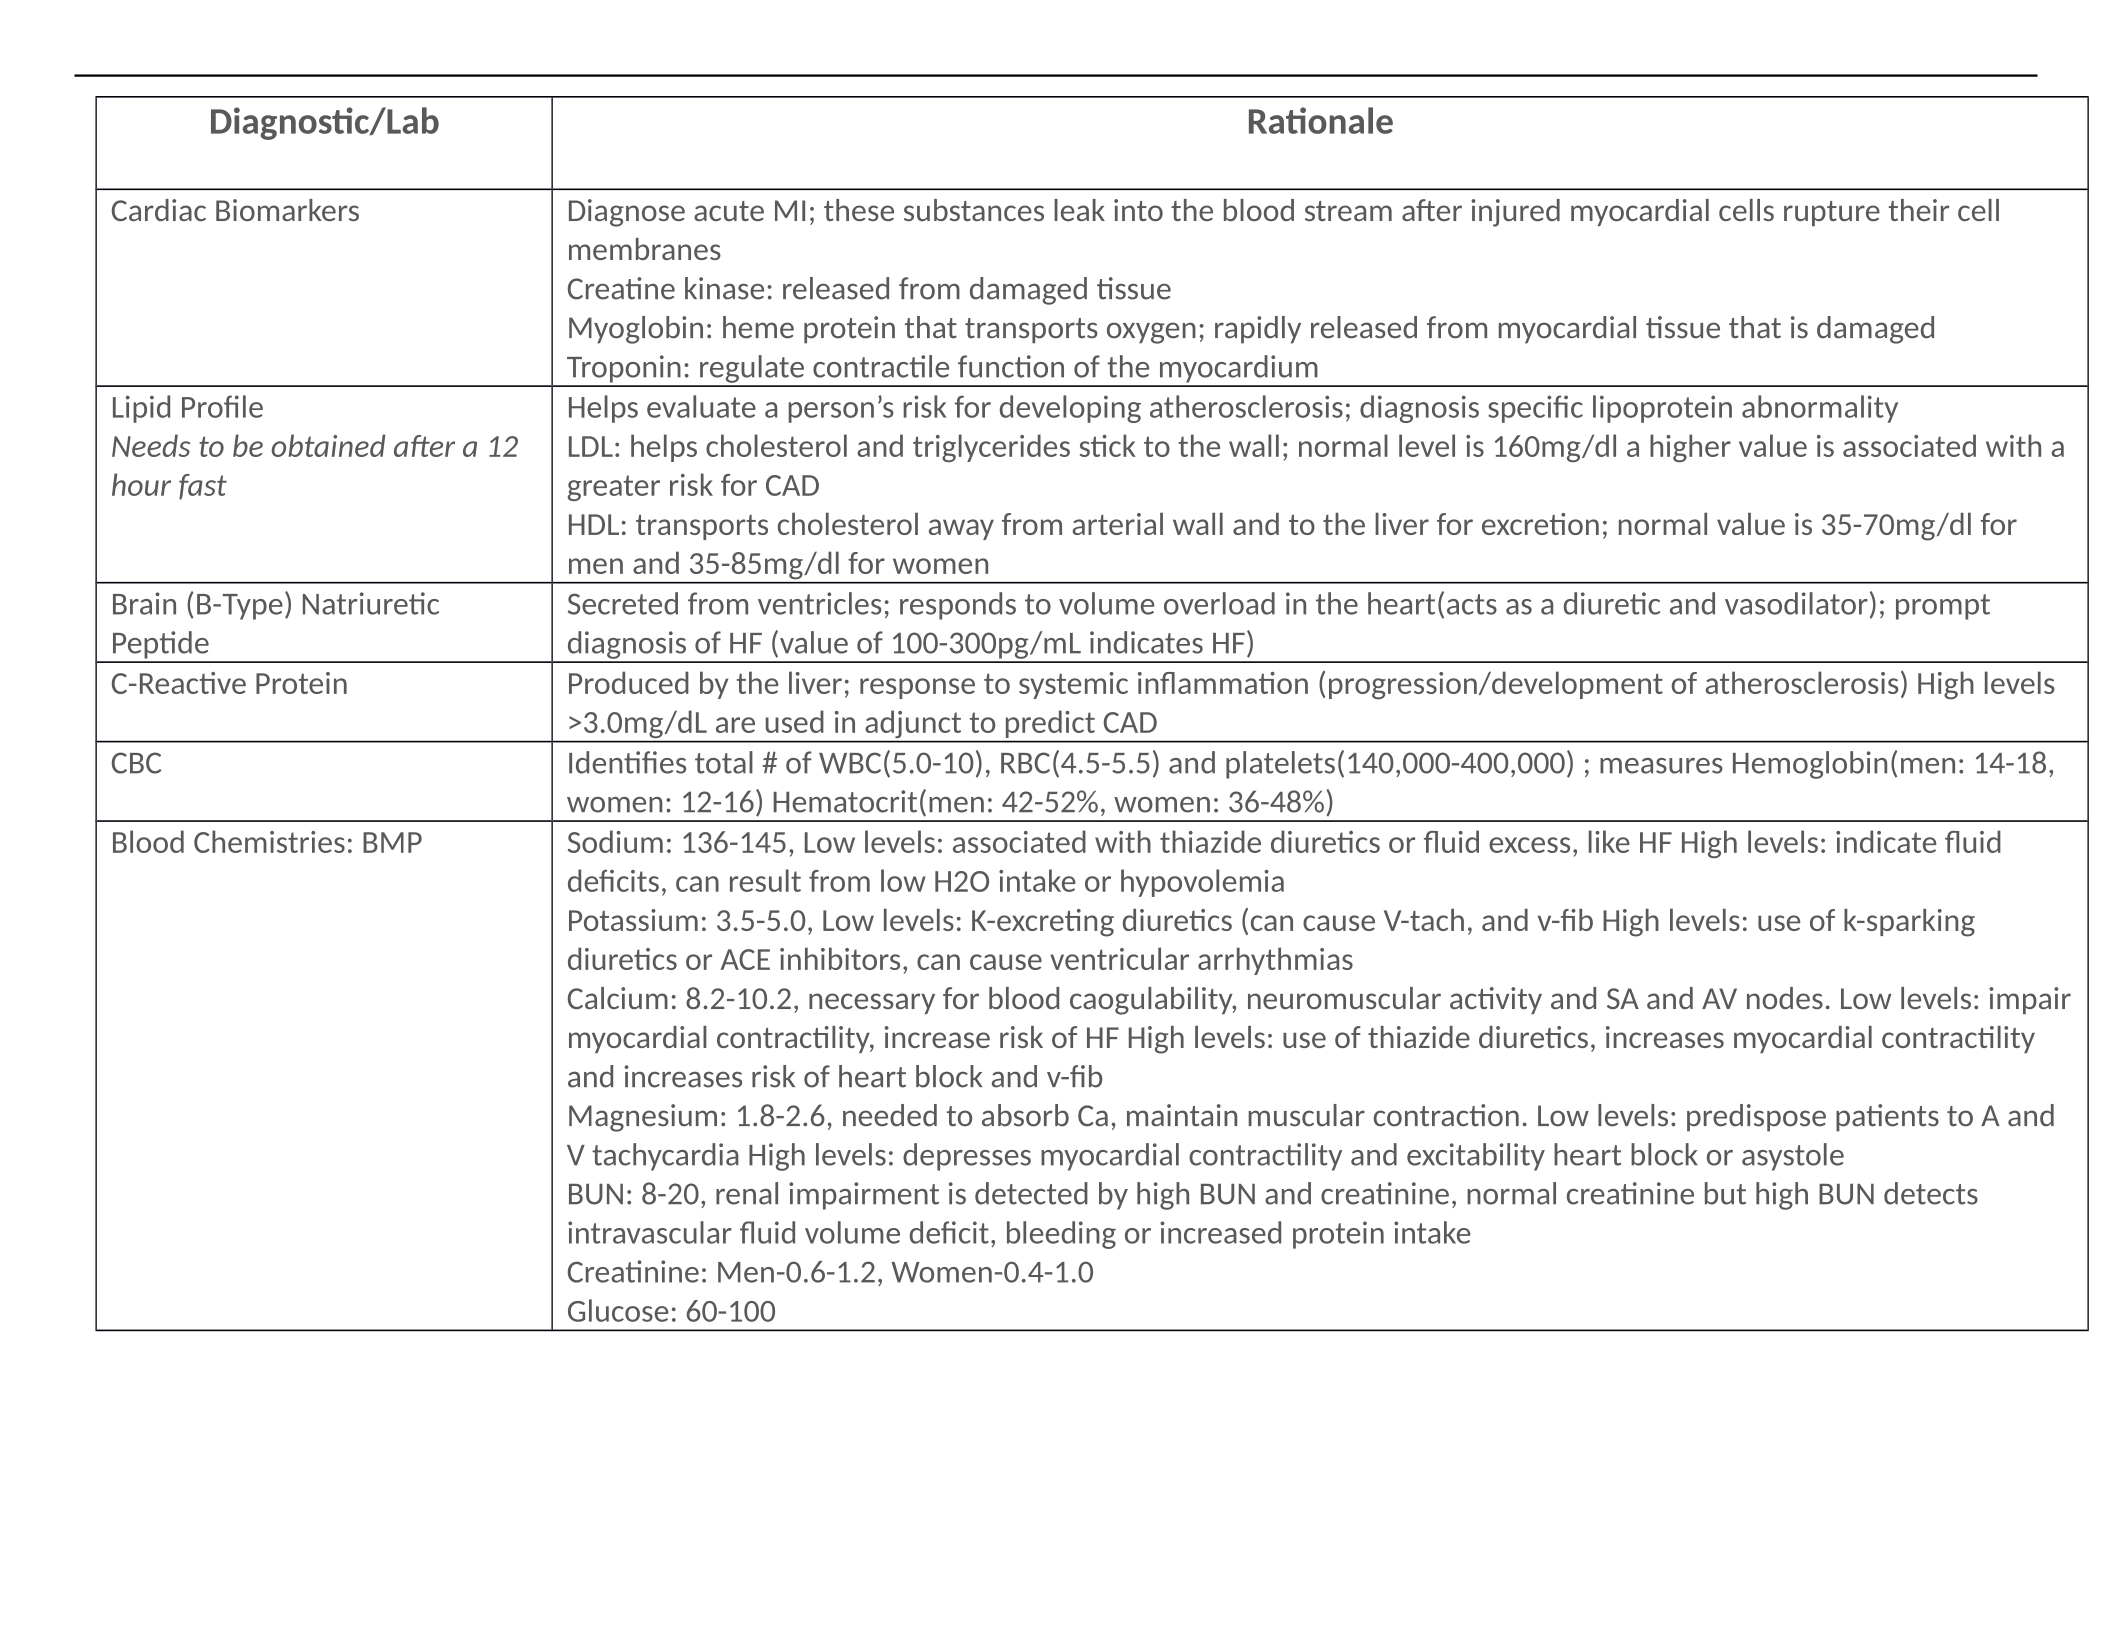
Diagnostic/Lab Rationale
Cardiac Biomarkers Diagnose acute MI; these substances leak into the blood stream after injured myocardial cells rupture their cell
membranes
Creatine kinase: released from damaged tissue
Myoglobin: heme protein that transports oxygen; rapidly released from myocardial tissue that is damaged
Troponin: regulate contractile function of the myocardium
Lipid Profile
Needs to be obtained after a 12
hour fast
Helps evaluate a person’s risk for developing atherosclerosis; diagnosis specific lipoprotein abnormality
LDL: helps cholesterol and triglycerides stick to the wall; normal level is 160mg/dl a higher value is associated with a
greater risk for CAD
HDL: transports cholesterol away from arterial wall and to the liver for excretion; normal value is 35-70mg/dl for
men and 35-85mg/dl for women
Brain (B-Type) Natriuretic
Peptide
Secreted from ventricles; responds to volume overload in the heart(acts as a diuretic and vasodilator); prompt
diagnosis of HF (value of 100-300pg/mL indicates HF)
C-Reactive Protein Produced by the liver; response to systemic inflammation (progression/development of atherosclerosis) High levels
>3.0mg/dL are used in adjunct to predict CAD
CBC Identifies total # of WBC(5.0-10), RBC(4.5-5.5) and platelets(140,000-400,000) ; measures Hemoglobin(men: 14-18,
women: 12-16) Hematocrit(men: 42-52%, women: 36-48%)
Blood Chemistries: BMP Sodium: 136-145, Low levels: associated with thiazide diuretics or fluid excess, like HF High levels: indicate fluid
deficits, can result from low H2O intake or hypovolemia
Potassium: 3.5-5.0, Low levels: K-excreting diuretics (can cause V-tach, and v-fib High levels: use of k-sparking
diuretics or ACE inhibitors, can cause ventricular arrhythmias
Calcium: 8.2-10.2, necessary for blood caogulability, neuromuscular activity and SA and AV nodes. Low levels: impair
myocardial contractility, increase risk of HF High levels: use of thiazide diuretics, increases myocardial contractility
and increases risk of heart block and v-fib
Magnesium: 1.8-2.6, needed to absorb Ca, maintain muscular contraction. Low levels: predispose patients to A and
V tachycardia High levels: depresses myocardial contractility and excitability heart block or asystole
BUN: 8-20, renal impairment is detected by high BUN and creatinine, normal creatinine but high BUN detects
intravascular fluid volume deficit, bleeding or increased protein intake
Creatinine: Men-0.6-1.2, Women-0.4-1.0
Glucose: 60-100
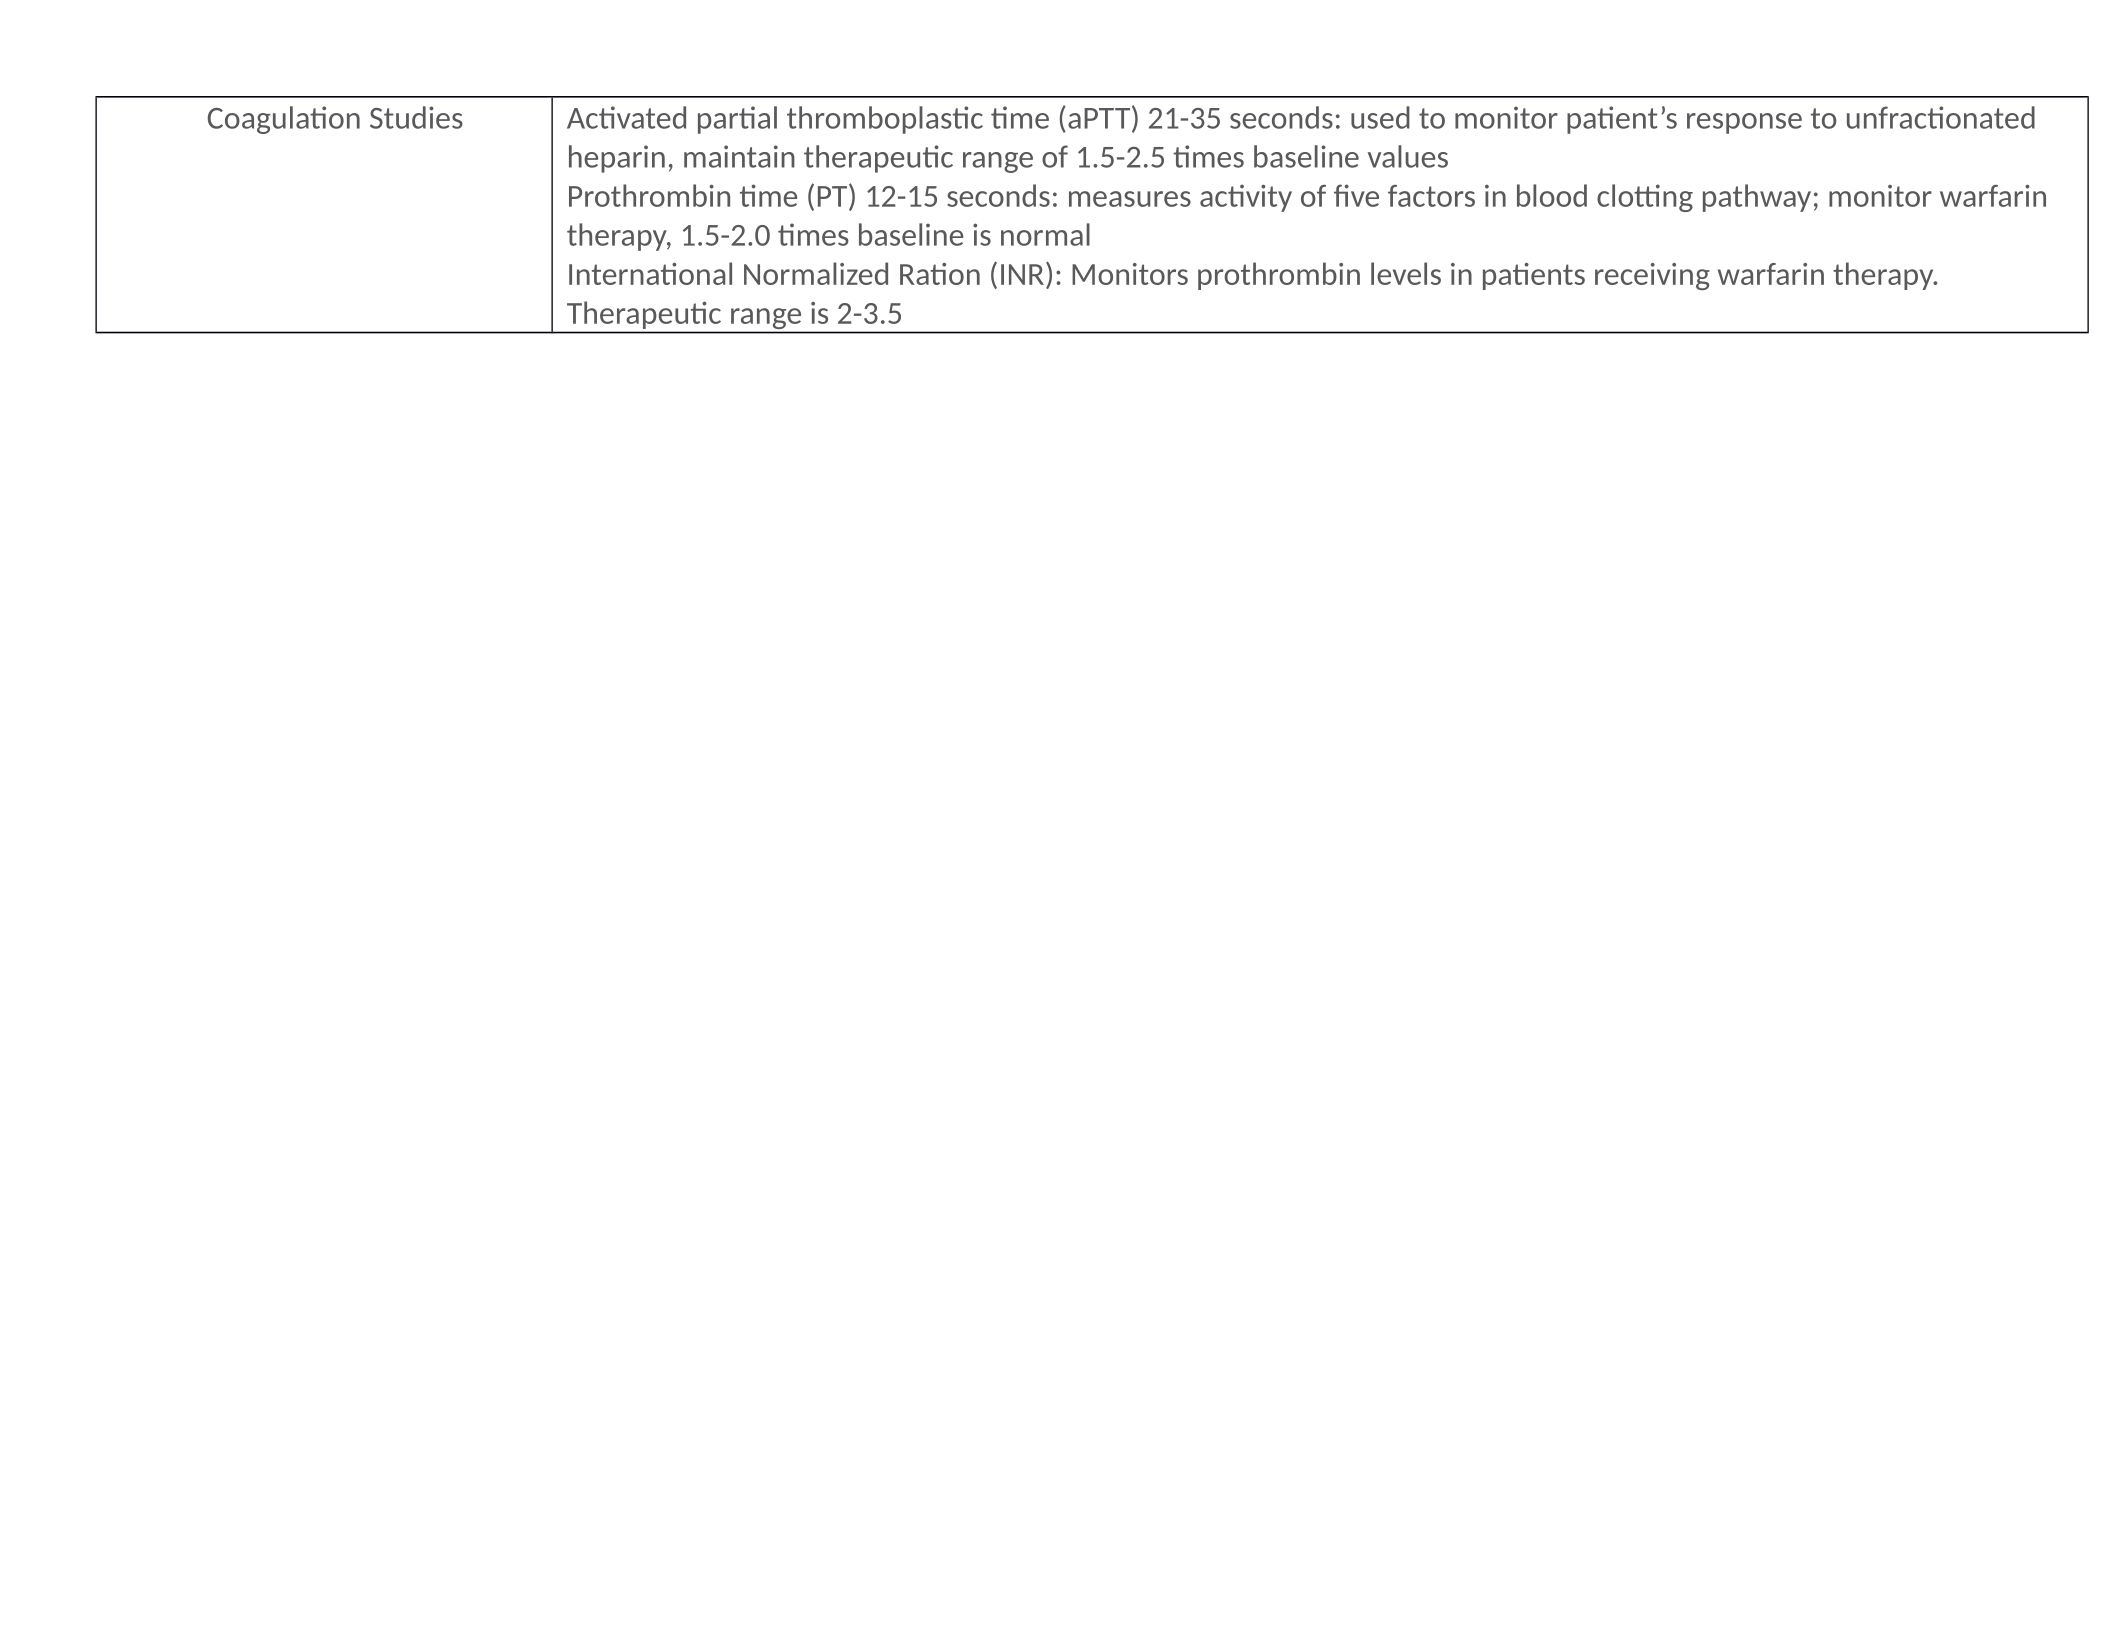
Coagulation Studies Activated partial thromboplastic time (aPTT) 21-35 seconds: used to monitor patient’s response to unfractionated
heparin, maintain therapeutic range of 1.5-2.5 times baseline values
Prothrombin time (PT) 12-15 seconds: measures activity of five factors in blood clotting pathway; monitor warfarin
therapy, 1.5-2.0 times baseline is normal
International Normalized Ration (INR): Monitors prothrombin levels in patients receiving warfarin therapy.
Therapeutic range is 2-3.5
Powered by TCPDF (www.tcpdf.org)

