


Child Language and Happiness Behaviors: Evaluating the Effects of Caregiver
Coaching
Caregivers often serve as their child’s first teacher, creating opportunities for
learning during interactions. Caregivers teach their infant how to communicate during
these interactions by establishing joint attention (e.g., pointing at a toy), modeling (e.g.,
labeling toys during play), and providing feedback (e.g., responding to the child’s
interests) (Owens, 2019). For example, infants initially reflexively cry, which is followed
by a response from their caregiver, such as a feeding or diaper change (Paul & Norbury,
2012). Over time, the infant begins to recognize that crying changes their caregiver’s
behavior, and in turn, they learn to communicate their needs (Lane & Brown, 2016).
Thus, caregivers shape a child’s short- and long-term communication. The transactional
language model is one way we can describe this early reciprocal relationship. This model
emphasizes the bidirectional nature of communication, meaning the adult and child
directly influence each other (Camarata & Yonder, 2002). Relatedly, the science of
behavior helps explain how behaviors continue or are extinguished by contexts.
Essentially, this means that if the child responds to the caregiver's communication, then
the caregiver's communication is reinforced, and their response back to the child will also
reinforce the child’s responding and/or initiating communication behaviors. Thus, when
practicing language skills during play, ideally, children will be happier and more likely to
reinforce their caregiver’s teaching behaviors as well.
Language development, a communication component, typically emerges later and
may be delayed for some children. Caregivers of children with expressive language
delays may struggle with supporting their child’s language development, especially when

2
children display difficulty reliably responding to their bids for attention. Caregiver
initiations may subsequently decrease because the child responds infrequently, or they
perceive that their child is disinterested. For example, parents and caregivers of children
with autism spectrum disorder (ASD) reported higher levels of stress when attempting to
address their child’s communication and language (Alpern, 2012; Benson & Karlof,
2009; Estes et al., 2009; Hayes & Watson, 2013). When this occurs, caregivers may need
support to know how to encourage their child to communicate using age-appropriate
language (Ledford & Wolery, 2013).
The Individuals with Disabilities Education Act (IDEA, 2004) ensures that
families with children at-risk for or with disabilities receive training, coaching, and
related supports within a family-centered approach to service delivery. Relatedly,
professional organizations recommend training caregivers to implement evidence-based
interventions (e.g., Division for Early Childhood of the Council for Exceptional Children,
2014), which increases the likelihood that children will maintain and generalize what
they learn (Sandall et al., 2005). However, caregivers may face barriers when securing
services. Logistical barriers can include location (e.g., living in a rural area),
transportation issues, and lack of childcare for other children. An access barrier is being
on a waitlist for services, especially when caregivers seek behavioral services. Finally, a
participation barrier may also hinder meaningful service delivery; some caregivers
reported feeling like passive participants in their child’s care (Brown et al., 2012; Farmer
et al., 2014) and, as such, are potentially ill-equipped to address their child’s
communication. Potential barriers may decrease opportunities for learning, especially
during critical developmental periods. For children with disabilities, it is crucial that

3
adults, including caregivers, provide an adequate dosage of opportunities to learn and
practice skills within natural routines and activities (Ledford & Wolery, 2013; Warren et
al., 2007). Thus, it is essential that professionals and caregivers collaborate and identify
practical and evidence-based practices in a timely manner to maximize child learning
opportunities (Dunst et al., 2000).
There is a breadth of research demonstrating practitioner success in training
caregivers to implement evidence-based practices in both clinical and home-based
settings (Rocha et al., 2007). Within this context, training refers to teaching a few skills to
a set criterion. In contrast, coaching refers to a collaborative process of setting goals for
practice implementation and a series of practice opportunities to implement procedures
and receive feedback during guided reflection (Snyder et al., 2015). Numerous training
and coaching interventions are available in published studies and related works (Brown &
Woods, 2012; Friedman, et al., 2012; Marturana & Wood, 2012; Powell & Dunlap, 2010;
Salisbury et al., 2018). These studies often include one or more of the following
components: (a) direct instruction, (b) modeling, (c) role-playing, (d) written/typed
scripts, and (e) feedback in-person or through video (Chaabane, et al., 2009; Cardon,
2012; Kaiser & Roberts, 2013, Lafasakis & Sturmey, 2007; Lane, et al., 2016; see Table 1
for detailed descriptions).

4
Table 1 Training and Coaching Components
Training
Component
Definition
Source
Direct
Instruction
(AKA,
Explicit
Instruction)
Direct instruction means a trainer
provides instruction over a specific
skill or concept using a highly
structured method. This typically
involves teaching specific steps within
a strategy and discussing when, how,
where, and why to use the strategy.
How can teachers effectively
teach study skills strategies?.
IRIS Center. (n.d.).
https://iris.peabody.vanderbilt.ed
u/module/ss1/cresource/q2/p03/
Chaabane, et al., 2009
Lane et al., 2016
Lafasakis & Sturmey, 2007
Modeling
Modeling means a trainer
demonstrates how the strategy is used,
often while verbally reviewing the
steps.
How can teachers effectively
teach study skills strategies?.
IRIS Center. (n.d.).
https://iris.peabody.vanderbilt.ed
u/module/ss1/cresource/q2/p03/
Chaabane, et al., 2009
Lane et al., 2016
Lafasakis & Sturmey, 2007
Role-
Playing
Role-Playing means a trainer provides
learners with opportunities to practice
their skills in a low-stakes or faux-
environment and receive feedback
before attempting the skills alone.
How can teachers effectively
teach study skills strategies?.
IRIS Center. (n.d.).
https://iris.peabody.vanderbilt.ed
u/module/ss1/cresource/q2/p03/
Chaabane, et al., 2009
Written/
Typed
Scripts
A written/typed script is a description
of a specific skill that functions as a
model or demonstration of the correct
response for the learner. These scripts
are typically practices again and again
until the skill is able to be used in-
vivo.
How can teachers effectively
teach study skills strategies?.
IRIS Center. (n.d.).
https://iris.peabody.vanderbilt.ed
u/module/ss1/cresource/q2/p03/
Chaabane, et al., 2009
Lane et al., 2016
Feedback
in-person or
through
video
Feedback refers to either in-person or
video-based responses from a trainer
to a learner that describes the positive
aspects of their behavior, as well as
areas of improvement. Feedback is
contingent upon the response provided
by the learner.
How can teachers encourage and
reinforce expected behaviors?
IRIS Center. (n.d.) IRIS | Page
6: Providing Positive Feedback
(vanderbilt.edu)
Chaabane, et al., 2009
Lane et al., 2016
Lafasakis & Sturmey, 2007
There are a variety of multi-component coaching interventions for caregivers who
want support for intervening on child communication (Ledford et al., 2019). The Family-

5
Guided Routines-based Intervention (FGRBI; Cripe & Venn, 1997; Woods et al., 2004),
Behavioral Skills Training (Shayne & Miltenberger, 2013), and Teach-Model-Coach-
Review (TMCR; Kaiser & Roberts, 2013) are all examples of packaged interventions for
families. FGRBI (Cripe & Venn, 1997; Woods et al., 2004) involves an intensive family-
centered approach (e.g., Problem Solving and Planning, Reflection and Review, etc.)
during weekly visits to help caregivers implement teaching opportunities in their natural
environment and daily family routines; the intervention may take up to 32 weeks for a
caregiver to reach mastery (Woods et al., 2004). BST is a widely used teaching
intervention and has been used to train caregivers to implement function-based
interventions (Shayne & Miltenberger, 2013). Although this training only included a
single instruction session (and maintenance sessions), the initial caregiver class lasted 3
hours (Shayne & Miltenberger, 2013). TMCR involves coaching caregivers to implement
enhanced milieu teaching language elicitation strategies (e.g., environmental
arrangement, responsive interaction, language modeling and expansion, etc.; Kaiser &
Roberts, 2013; Wright & Kaiser, 2017). TMCR involves an initial workshop, followed by
approximately 12 weeks (about 3 months) of training, twice a week and for 40 min per
visit (Roberts et al., 2014). Ideally, caregivers will receive coaching for an extended
period, but accessing specialized interventions, as well as barriers, may delay
implementation and be problematic, especially if caregivers lack foundational skills for
encouraging communication and teaching language.
Caregivers of children with delayed language need timely access to services and
supports that can help them provide their children with a rich environment for language
development. A potential option to fill this need is by conducting relatively brief coaching

6
interventions targeting caregivers' foundational skills. An example of this is the rapid
coaching intervention (RCI) described by Lane and colleagues (2016), which found that a
multi-component RCI was effective for teaching caregivers naturalistic language
strategies to use with their child with ASD during play. Naturalistic language strategies
refer to practices caregivers can use to promote language by altering their child’s natural
environment, such as the following skill sets: playing, noticing and responding, providing
linguistic input, and planning communication opportunities. These skills are commonly
recommended to caregivers because they are basic and foundational skills that may help
the caregiver promote motivation and engagement from their child, while also providing
models of new play routines and contrived opportunities for their child to practice
communication. The RCI was originally developed to support families seeking additional
support and services. The intervention includes a rationale for each caregiver behavior,
in-vivo coaching during short sessions, and immediate feedback. Because of limited
resources, the intervention was designed to help caregivers learn strategies they can use
across contexts that may lead to long-term improvements in communication. This
intervention has been utilized in homes (Zhu et al., 2022), online (Lane et al., 2023), and
in community-based clinics, with support from a speech-language pathologist (Campbell,
2022; Reiss, 2023). In a recent study (Gullett, 2024), caregiver feedback (e.g., watching a
feedback video was nonpreferred) highlighted the importance of potentially tailoring
training and coaching by family instead of an identically packaged intervention. Previous
literature also highlights the importance of tailoring performance feedback systems
(Barton, et al., 2011). This is also an important consideration when further evaluating the
proposed RCI.

7
An important aspect of caregiver-focused interventions, including the RCI, is
considering the impact on the child. For example, communication and language
interventions for young children often include measures of communication, such as
nonverbal behaviors (e.g., gestures), linguistic competence (understanding language), or
linguistic performance (using language) (Lane & Brown, 2016; Owens, 2019). Additional
child behaviors may warrant attention in such studies. For example, child communication
is often measured during play because the context is considered a natural part of early
childhood and may increase a child’s motivation to communicate. Ideally, we can expand
our understanding of these underlying assumptions by including measurements of the
child's happiness during play, especially when caregivers are coached by another adult on
naturalistic strategies. Assessing child happiness can also allow researchers to observe if
the children enjoy the intervention, an important but often overlooked aspect of an
intervention’s social validity. Historically, research in adults often uses self-report
measures of emotions such as happiness (e.g., Logan et al., 1998). Self-reported
happiness in adults is associated with increased productivity and social engagement
(Diener & Seligman, 2002; Judge et al., 2001), as well as increased creativity and
cognitive flexibility (Baas et al., 2008; Bless et al., 1992; Fredrickson & Branigan, 2005;
Ritter & Ferguson, 2017). Given the potential benefits of happiness, expanding measures
to early childhood research may be useful for professionals.
Regarding happiness, increased awareness of the lived experiences of
neurodivergent individuals is important, especially when considering self-reports of what
happiness looks like, which has direct implications for professionals. Happiness is often
defined through either a self-report of well-being or observing a positive affect

8
(emotional) state (Haybron, 2020). Within relatively brief studies, it may be more feasible
and practical to measure happiness as a positive emotional state of an individual, rather
than “well-being” (i.e., long-term measure). Previous researchers have developed the
Indices of Happiness and Unhappiness Questionnaire to assist in making treatment
preference and decision-making for nonverbal and minimally verbal individuals (Parsons
et. al., 2012, Ramey et al., 2023). Individualized indices were created by providing
relevant adults (caregivers, teachers, etc.) with a brief questionnaire about the behaviors
the child exhibits when happy and unhappy. Caregivers completed the questionnaire and
reported behaviors representing happiness in their child. Operational definitions of
happiness behaviors are then developed using the results.
Measures of happiness behaviors have informed assessments and interventions,
including functional analyses and derived treatment plans (Dillon & Car, 2007; Thomas
et al., 2021). Being able to analyze and identify happiness behaviors is thought to make
an individual’s preference indication more genuine and robust (Green et al., 1988,
Parsons, et al., 2012, Smith et al., 2005). Therefore, analysis of happiness behaviors may
improve language assessment and treatment by helping practitioners better understand
their client’s preferences.
Additionally, researchers have used measurements of happiness behavior to assist
in determining which teaching interventions to use when working with children with
ASD (Dunlap & Koegel, 1980). However, measuring the children’s indices of happiness
has not previously been used to evaluate the social validity of caregiver training and
intervention services.

9
The purpose of this study was to evaluate the effectiveness of a tailored RCI
(training and coaching) with caregivers of children with developmental disabilities. This
study replicated Lane et al. (2016) and includes components from other studies (e.g.,
Campbell, 2022) and recommendations (Gullett, 2024; Lane, 2023). Like other studies,
this study involved evaluating child-level communication but extended child measures by
including an assessment of happiness behaviors to assess the social validity of caregiver
coaching interventions.
Research Questions
1. Primary research question: When a tailored RCI is used during caregiver-child
play sessions, will caregivers reliably implement naturalistic strategies with
fidelity?
2. Secondary research questions: When a tailored RCI is used during caregiver-
child play sessions, will child happiness behaviors increase? Furthermore, will
children display increases in vocal communication in the form of responses and
initiations after caregivers learn naturalistic strategies?

10
Method
Participants
One caregiver-child dyad was recruited for this study. The study-level inclusion
criteria were that the caregiver was (a) at least 18 years of age, (b) the primary caregiver
to a 1-4-year-old child with expressive language delays (defined as scoring below the 25th
percentile on the MacArthur-Bates Communicative Development Inventories [MCDI]),
and (c) fluent in written and spoken English. Participation also required that the caregiver
have access to Wi-Fi and be able to join live online Zoom links for sessions. Potential
participants were excluded from the study if their child recurrently demonstrated high-
risk or dangerous challenging behaviors (e.g., physical aggression toward others, high-
magnitude self-injury, etc.). A caregiver interview and pre-screening observation occurred
to ensure that the caregiver and child met the inclusion criteria. The pre-screening also
included administering the MCDI (Marchman et al., 2023) to the caregiver and collecting
a language sample on the child’s communication skills. The MCDI is a reporting
instrument for caregivers to describe their child’s early language abilities; caregiver
ratings are converted to fitted percentiles. This informed the team on the frequency and
type of words frequently used by the child.
The caregiver-child dyad consisted of Jordyn, an African-American female in her
late 30’s, and her biological son, August, an African-American, 32-month-old male.
Jordyn and August’s father also have three older daughters who live in their home with
them. Jordyn found out about the study from recruitment efforts at August’s preschool.
August has the following diagnoses: autism spectrum disorder, level three, global
developmental delay, hypotonia, and expressive communication delay. Jordyn reported

11
that August used mostly gestures such as pointing or guiding another person’s hand to
communicate, as well as a handful of names (Mom, Dad, Gi-Gi, sister) and single-
syllable babbling. August often babbled with a social function, trying to communicate,
especially during back-and-forth exchanges with his mom. During play, August mostly
engaged in physical activities and routines (tosses, tickles, clapping, etc.). Observations
indicated that August’s play was primarily sensorimotor (i.e., sensory exploration of toys)
and relational (i.e., combining objects by grouping, building, or associating objects
differently; Ledford et al., 2019) play. August attended preschool five days a week and
received early intervention services, including speech therapy once a week.
The researcher was a 24-year-old White female graduate student. At the time of
the study, she was enrolled in an Applied Behavior Analysis master’s program.
Previously, the researcher received her Bachelor of Science degree in Psychology and
Applied Behavior Analysis. The researcher was also the primary interventionist and data
collector and will be referred to as the researcher. Additional graduate students in the
same Applied Behavior Analysis program served as secondary data collectors. Secondary
data collectors had at least two years of experience teaching and/or working directly with
individuals with disabilities.
Settings & Materials
This study was conducted through telehealth appointments using the web app
Zoom Video Communications, Inc. (i.e., Zoom). All sessions took place via Zoom in a
bedroom in the participants’ homes, typically using the bed as a sitting/play area. The
caregiver brought some play materials and toys into the room before the sessions began

12
and placed them within the sight of the child. Play materials were sometimes placed
within the child’s reach and sometimes out of reach.
All sessions were recorded via Zoom and using the researcher and data collector’s
computers. Data were collected by using the session recordings to track how many and
when caregiver and child target behaviors occurred. Laptops were needed to provide the
caregiver with training examples and feedback, as desired by the caregiver. The caregiver
was trained and coached on 3-4 sets of behaviors or skills to promote communication in
their child. The caregiver is currently being coached on the second set of skills. Each
asynchronous skill training consisted of a training video and corresponding handout.
Training videos described a naturalistic strategy, provided a rationale for using the
strategy, and provided a video model/example of a research team member using the skill
during a child play session. The training videos also demonstrated how these skills build
on one another by incorporating the previously taught skills into new skill lessons to
promote maintenance of old skills. During coaching sessions, the researcher briefly
reviewed the training materials and answered any caregiver questions before beginning
play sessions/observations. The researcher incorporated tailoring options into the
caregiver training procedures including asking the caregiver their preferences on
feedback level and methods (Appendix A)
Measurement System & Behaviors
Event recording with time stamps was utilized to record caregiver and child
behaviors. Event recording with time stamps is more precise than count alone because it
captures the exact moment each behavior occurred (Ledford et al., 2018). Data collectors
had a list of target adult behaviors, which were recorded with a timestamp on data sheets

13
(Appendix B). For happiness behaviors, data collectors were provided individualized
indices of happiness and unhappiness to record target child behaviors, which were
recorded using momentary time sampling (10s intervals) on datasheets. Additional
secondary dependent variables were recorded using a pre-and post-test. These data were
collected using the baseline play samples (responding to caregiver, and child initiation).
Primary Dependent Variables – Adult
The primary dependent behaviors were first developed by Lane et al. (2016) and
further refined in an unpublished training guide developed by Lane (2023). The four skill
sets are summarized below; full definitions are attached in Appendix C.
Set 1: Playing
This set focused on teaching caregivers play skills targeted at promoting their
child’s engagement. These skills let the child know that the adult is interested in what
they are playing with and to model new novel play skills and routines.
Imitation. The target behavior imitation included any instance where the
caregiver replicated the child’s action on objects or play routines. The adult’s imitation
must have occurred with the same, similar, or pretend play materials. For example, if the
child rocked a baby doll, then the caregiver should have picked up a doll or pretended to
have one and rocked it similarly to be considered imitation. However, adults could have
also pantomimed actions if no extra materials were available. Separate instances of
imitation were recorded when different toys were used, different actions occurred, or
more than 3 s passed in between actions.
Expansion. This skill included anytime the caregiver added new toys or actions
to the child’s play to diversify or expand the child’s play routines and behaviors.

14
Expansions had to happen within 3 s of the child engaging in the initial play behavior.
Additions also to be thematically or contextually relevant to the child’s current play
behaviors and routines.
Set 2: Noticing and Responding
This behavior required the adult to notice all forms of their child’s communication
and respond meaningfully.
Responding to Communication. This behavior was defined as “caregiver
vocally responding to the child’s communication within 1-3 s [with a contextually
relevant and grammatically correct sentence] and waiting up to 5 s for a child-level
response” (Lane, 2023, p. 17). Examples included the child gesturing or verbalizing and
the caregiver responding by providing language related to the child’s gesture (e.g.,
pointing to a stuffed giraffe) or repeating and adding to the child’s verbalization (e.g., the
child said “car” and the caregiver responded with “roll the car”).
Set 3: Providing Linguistic Input
Skill set 3 and subsequent skills have not been taught yet. The following
behaviors will be targeted later, as the caregiver meets mastery criteria for each skill set.
The unit 3 training materials were shared with the caregiver on April 8th and coaching
sessions will begin this week. When the child is not communicating, the caregiver can
provide input, or model language in the form of contextually relevant and grammatically
correct sentences.
Describing the Child’s Play. This behavior refers to the caregiver providing a
verbal model in the form of a relatively brief and grammatically correct sentence that
described the child’s play actions and then waited up to 5 s for the child to respond.

15
Examples include a caregiver saying, “The baby is sleeping,” while their child rocks a
baby doll. Non-examples include the caregiver asking questions or making several
comments successively, with little to no time for a response.
Caregiver Describing Their Own Play. This behavior refers to the caregiver
using a verbal model, like above, to describe their own play and waiting up to 5 s for the
child to respond. The caregiver’s play must be contextually relevant, meaning that the
caregiver should imitate the child’s play or take a turn in the child’s play routine, not
doing and describing random independent activities. An example could be the caregiver
saying, “I am drawing a flower,” while taking a turn or simultaneously drawing with
chalk with their child and then waiting.
Set 4: Planning Communication Opportunities
The primary focus of this skill is to teach the caregiver how to create
opportunities for communication for their child.
Environmental Arrangement (EA). EA refers to the caregiver providing
opportunities for communication (e.g., placing preferred objects in view but out of reach),
specifically encouraging the child to use the target language, and waiting up to 5 s for a
verbal response. If the child uses the target language, communicates otherwise, or
displays sustained interest, the caregiver responds by providing the corresponding
consequence (e.g., access to an item, social attention). If the child loses interest, the adult
ends the trial and tries again later in the session.
Secondary Dependent Variables
Responding to Caregiver

16
Responding to a caregiver was operationally defined as any attempt by the child
to communicate verbally or nonverbally (i.e., point, show, reach) within 5 s of a
caregiver’s question, cue, or prompt. Any verbalization, approximations, and non-word
sounds were considered an attempt to communicate. Only the first instance was counted
if a child repeated the same word or phrase repeatedly unless there was more than a 3-s
delay between the ending of the first word and the beginning of the second one.
Examples included the child imitating a caregiver modeling target language or reaching
towards the item the caregiver modeled, the child saying or approximating the name of a
toy the caregiver is holding, and the child saying “no” or using vocalizations. A non-
example was if the child independently initiated communication.
Initiating to the Caregiver
Initiating to the caregiver was defined as any spontaneous verbal or nonverbal
attempt to communicate, including any words, vocalizations, or gestures the child
engaged in during sessions. Initiations were counted if more than 5 s had elapsed since
the caregiver provided a question, cue, or prompt to communicate. Like responding, only
the first vocalization was counted if the child repeated the same word or phrase over and
over unless there were more than 3 s between the ending of one word and the beginning
of another. Examples included the child giving the caregiver a toy to play with, guiding
the caregiver to a toy they cannot reach, or asking to be tickled. Non-examples of
initiation to a caregiver included a child approaching their caregiver after their caregiver
spoke to them or a child handing something to their caregiver when their caregiver
gestured for it.
Happiness Behaviors

17
Happiness behaviors were defined as observable facial or vocal responses, such as
laughing and smiling, and are unique to all children. Happiness indices were defined
individually for the child, corresponding to standards offered in previous literature
(Dunlap & Koegel, 1989; Green & Reid, 1996; Parsons et al., 2012; Ramey et. al. 2023).
The researcher administered an altered Indices of Happiness and Unhappiness
Questionnaire (Appendix D) to the caregiver and developed an individualized list of
happiness and unhappiness behaviors for the child. The researcher added additional
questions to the questionnaire regarding the child’s joint engagement. Engagement was
added as a variable to account for times when the child may be happy or content, but not
outwardly expressing it through their behavior. Even when we are feeling happy, we do
not engage in happiness behaviors non-stop (e.g., people may laugh or smile for a few
minutes of conversation, but also engage in neutral or focusing behaviors). Therefore,
engagement was seen as a neutral or semi-positive state to reflect when the child was
interested in play and accepted their caregiver playing with or near them. Each happiness
and unhappiness behavior from the list was operationally defined and written out for data
collectors (Appendix E). Happiness and Unhappiness behaviors were tracked separately
using momentary time sampling (not mutually exclusive: could happen at different times,
the same time, or neither could be happening).
Since outward expressions of happiness can be fleeting and difficult to capture,
the researcher added a joint-engagement component to the indices of happiness. To better
capture and conceptualize happiness, the researcher provided an operational definition of
joint engagement and no joint engagement for August to the happiness/unhappiness
datasheet (Appendix E). These definitions were created using information collected

18
during the interview and administration of the altered Indices of Happiness and
Unhappiness Questionnaire (Appendix D). Data collectors used the same momentary
time sampling datasheet to indicate happiness, unhappiness, and joint-engagement
behaviors across all sessions.
Happiness, unhappiness, and joint engagement behaviors were collected and
assessed across all baseline and intervention sessions. Intervals were 10 s long, and all 4-
min sessions had a total of 24 intervals. Potential examples of happiness behavior
included: smiling, laughing, hugging, jumping, giggling, or hand flapping. Potential
examples of unhappiness behaviors include crying or property disruption.
Experimental Design
The RCI was evaluated using a multiple baseline across behaviors design (Gast et
al., 2018). Multiple baseline designs involve a time-lagged introduction of the
intervention at different points in time. Each tier represents a different caregiver
behavior/skill they have learned, and the order of the tiers was established based on the
complexity of the target behaviors (i.e., discrete skills first, chained skills last). To move
from one tier to the next tier, (1) the adult must first meet the pre-determined criterion,
and (2) baseline data for other skills shows a stable response pattern. Researchers only
intervened on one skill/tier at a time, creating a time lag between intervening on skills
based on the caregiver’s behavior. This design was chosen because the research question
for this study is a demonstration research question that investigated likely non-reversible
behaviors (Lane et al., 2016; Ledford & Gast, 2018, p. 97-131). This design did not
require removing an intervention to demonstrate a functional relation; the caregiver’s
performance was used to make experimental decisions. Additionally, this design allows

19
the research team to discover any covariation in untreated tiers by having continued
baseline data collection. Since the caregiver was learning to implement various
responsive interaction strategies, monitoring for potential changes to other behaviors/tiers
was vital. Data were collected continuously throughout every session on caregiver and
child behavior. Continuous measurement of pre-intervention behaviors allowed the
research team to examine the data more regularly than a multiple-probe design (Gast et
al., 2018). A multiple-baseline design was used to time-lag the introduction of the RCI
across two caregiver behaviors, each at a different point in time. The researcher will
continue to implement the RCI with the family across an additional two caregiver
behaviors/tiers.
Since caregiver behavior, specifically meeting the mastery criterion for a
behavior, determined when the intervention was introduced to other behaviors, adult
behavior was the primary dependent variable. Changes in child behavior did not impact
experimental decisions; therefore, child behaviors were considered secondary dependent
variables. This design helped detect and control for maturation, history, testing, multi-
treatment interference, and instability by continually collecting data in each condition
until stability was observed in the data path. Secondary observer data collectors were
trained until they reached a pre-determined criterion to control for threats to procedural
infidelity and instrumentation. Functionally independent behaviors were selected to
decrease the possibility of covariation (Gast et al., 2018).
Procedures
Screening & Baseline Condition

20
Before the first appointment, the caregiver completed the MCDI: Words &
Gestures, Third Edition, using the form corresponding to their child’s age (Marchman et
al., 2023). The purpose of this form was for caregivers to indicate their child’s vocabulary
and related age-expected language. During the initial meeting, the researcher interviewed
the caregiver and administered the altered Indices of Happiness Questionnaire (Appendix
D). Due to a scheduling conflict, the child was unable to attend the first meeting and the
remaining screening/baseline procedures were postponed until the second meeting.
At the beginning of the second meeting, the researcher asked the caregiver how
the child’s day had been. This verbal caregiver report was collected across all baseline
and intervention meetings to account for any drastic variability in child behaviors across
different meeting sessions. During the second meeting, the researcher told the caregiver
to play with her child as she normally would. Then, the researcher started recording on
her computer, set a timer, and observed the caregiver conduct a 15-minute play session
with their child. This caregiver-child play session was utilized as a language sample to
assess how the child normally communicates. The recording of the language sample was
then transcribed and analyzed (see Appendix F). When measuring vocal communication,
approximations of words/language were included, and approximations were defined as
having at least one phoneme from a word(s) related to the referent (Paul & Norbury,
2012). Results of the language sample indicated that the child said 11 intelligible words
and 5 novel words during the sample. Additionally, the mean length of utterances in
morphemes (MLUm) and words (MLUw) were 1.08, respectively. This score fell into the
1.00-2.00 range and is correlated with the first of Brown’s five stages of development
(Brown, 1973). Children scoring in the first stage of Brown’s language development scale

21
indicate a child should have or be progressing toward a vocabulary of around 50-60
words (Brown, 1973).
Following the meeting, the implementor met with an SLP to discuss the
assessment data and language sample and to identify child-level instructional targets.
Before beginning coaching sessions, the caregiver was informed of the child’s
communication targets, the rationale behind each target, and how to promote and
reinforce their child’s target communication behaviors.
The 15-min play session was trimmed down to a 12-min sample (three 4-min
sessions), which was coded and analyzed to assess the caregiver’s existing
skills/behaviors. Caregiver behaviors that occurred 25% or less of the session (no more
than once every 4 min) were considered for the study. This screening session also served
as the baseline condition (three 4-min sessions). Three baseline sessions were completed,
and no further sessions were needed because data was stable. Procedures for the
screening/baseline sessions were as follows:
1. Asked/Prompted the caregiver to set up the room/area with preferred toys.
2. Instructed the caregiver to play with their child like they normally would and
to follow the child’s lead.
3. Researcher provided no further instructions or prompts to the caregiver or
child.
Intervention Condition
The implementor, caregiver, and child all met via Zoom together. RCI sessions
occurred approximately once a week for 1-hr. The caregiver received and reviewed an
asynchronous training module on each target behavior before beginning coaching

22
sessions on the corresponding behavior. At the beginning of the first intervention session,
the researcher explained the child’s language target and a rationale for each target.
Additionally, the researcher asked the caregiver how the child’s day had been. This verbal
caregiver report was collected at the beginning of all intervention meetings to account for
any drastic variability in child behaviors across different meeting sessions. This was
important for happiness data stability because multiple sessions were completed within
each meeting, which could lead to cyclical data or major differences in happiness
behavior across different days.
During sessions, the implementor briefly reviewed the training materials
(described below) with the caregiver, discussed the rationale for the target behavior,
offered to show clips (examples) of how to engage in the behavior, offered to demonstrate
or role play with the caregiver, and answered any caregiver questions. Following the
review, the implementor asked the caregiver to practice the skill with her child and
conducted multiple 4-min coaching sessions for the remaining duration of the visit. The
implementor recorded each coaching session individually and provided live performance
feedback on the caregiver implementing target behaviors (e.g., “Great job adding new
actions to August’s play!” “Awesome job waiting, that was perfect!”). After each session,
the implementor offered to replay parts of the recording to provide positive feedback
regarding the caregiver’s use of the target behavior and identify times they could have
used it. The learning criterion for each skill was the caregiver displaying the behavior at
least four times per session and across three consecutive sessions.
Caregiver Training. The implementor sent an asynchronous training link to the
caregiver via email a few days before the first coaching session for each tier. For each

23
skill, a link provided the caregiver with a handout about the skill and a short training
video. Each training handout defined a target caregiver skill and provided guidelines for
how often they should engage in the behavior (See Appendix G). Training videos were
each between 5-8 minutes long (Lane 2023) and provided a definition of the skill, a
rationale for using the skill, guidelines for how often to use the skill, and an example of a
research team member modeling the skill with a child.
Coaching Sessions. Right after the implementor reviewed the training materials,
the researcher and caregiver began coaching sessions. The researcher began each session
by asking the caregiver to practice the target skill with their child. The researcher
provided behavior-specific praise after each instance of caregiver target behavior. The
session was recorded directly onto a computer by either the researcher or the secondary
data collector. The researcher asked the caregiver at least once per meeting session about
the frequency and type of feedback provided to her and her feedback preferences.
Post-session Feedback. Following each coaching session, the researcher
immediately provided performance feedback. Performance feedback included praising
specific instances of skills, summarizing the live coaching feedback, and providing any
additional commentary (e.g., explaining why a specific instance did not count). An
example of performance feedback included the researcher saying, “You did a great job
noticing and responding when August gestured to go up- it's great that you’re responding
to all of his forms of communication!” (Specific praise), “I noticed that you used the new
skill several times throughout- you did an amazing job!” (Summarizing live coaching
feedback), “Don’t forget to wait for five seconds after your sentence so he has a chance to
respond or mimic you” (additional commentary). Next, the researcher asked the caregiver

24
how they felt the session went and if they had any questions during the post-session
feedback. After answering any questions, the researcher offered to show the caregiver
specific examples from the video recording. The researcher also offered to model the skill
live and/or rewatch portions of the training video with the caregiver. Performance
feedback is estimated to take 2-3 min (Lane et al., 2016).
Maintenance Condition
Maintenance sessions will occur one week after the caregiver has reached the
mastery criterion for all target behaviors. Maintenance sessions will be conducted via
Zoom and will be the same, procedurally and contextually (similar toys, arrangement,
etc.), as baseline sessions. The researcher will not provide feedback during maintenance
sessions. Additionally, the multiple-baseline design ensures that maintenance data is
taken on all initial tiers while implementing the intervention in later tiers. Thus, the
nature of the design will allow us to track maintenance data on early tiers throughout the
study.
Social Validity
After the study concludes, social validity will be evaluated by conducting a
caregiver interview. The interview will be conducted by someone unaffiliated with the
intervention team to ensure that the caregiver is comfortable discussing their experiences
in the study. Questions include:
1. Tell me about your experience with this study, such as your thoughts on the
training videos, online coaching, feedback, etc.?
2. Given what we just discussed, how can we better support families in the future?
3. Tell me about [child’s name]’s experience.

25
4. Can you tell me about any times you have been able to use these skills outside of
our time together?
5. Will you continue to use any of these strategies after this study?
Reliability & Fidelity
Interobserver agreement (IOA) and procedural fidelity data were collected for at
least 33% of sessions across every condition. Before assisting with the study, secondary
data collectors were trained on relevant data collection procedures (procedural fidelity,
caregiver behaviors, child happiness behaviors, and child communication behaviors).
Data collectors were trained by being provided (a) definitions of target behaviors and
procedures, (b) opportunities to practice, and (c) performance feedback. Training
continued until data collectors had at least 90% agreement on target behaviors (Ledford et
al., 2018).
Interobserver Agreement
Data collectors utilized datasheets and session recordings to rewatch and time-
stamp video records on caregiver and child behavior. Video records was coded via time-
stamps in an Excel spreadsheet or using datasheets. IOA was analyzed using point-by-
point agreement with timestamps. Time stamps needed to be within 5 s of one another to
count as an agreement for instances of target behavior. The IOA was calculated as the
number of agreements within the time frame divided by the number of agreements plus
disagreements, with the quotient multiplied by 100 (Campbell, 2022; Ledford et al.,
2018). If IOA data had fallen below 80%, data collectors would have been retrained until
they reached the criteria previously listed. IOA for caregiver behaviors was 100 % across
all conditions (baseline and intervention). IOA for child happiness ranged from 94% to

26
97%, with an average of 96%. IOA for child communication behavior has not yet been
calculated or analyzed.
Procedural Fidelity
Data collectors used data sheets and meeting recordings to collect procedural
fidelity; copies of these data sheets are listed in Appendix H. The occurrence and
nonoccurrence of the primary researcher’s behavior was recorded as procedural fidelity.
The researcher was scored on the following behaviors, as well as other behaviors across
conditions: provide the caregiver with (a) the rationale, (b) a video model of the target
behavior, (c) behavior-specific praise during coaching sessions, and (d) examples and
realistic suggestions during feedback sessions (Appendix H). Procedural fidelity was
calculated as the number of observed behaviors divided by the total number of planned
behaviors multiplied by 100 (Ledford et al., 2018). Procedural fidelity across conditions
ranged from 93-100% across all conditions (baseline, tier 1, and tier 2), with an average
of 99% across conditions.

27
Results
All graphed data were visually inspected within and between conditions, with
consideration of level, trend, stability/variability, overlap, immediacy of effect, and
consistency of effect (Ledford & Gast, 2018). Stability within conditions and differences
across conditions are essential aspects of visual analysis of time-lagged graphs. For the
caregiver behavior, a functional relation is defined as at least three demonstrations of
effect (i.e., therapeutic improvements in a target behavior in the intervention condition
compared to performance in the baseline condition), with no more than one non-effect
(Barton et al., 2018).
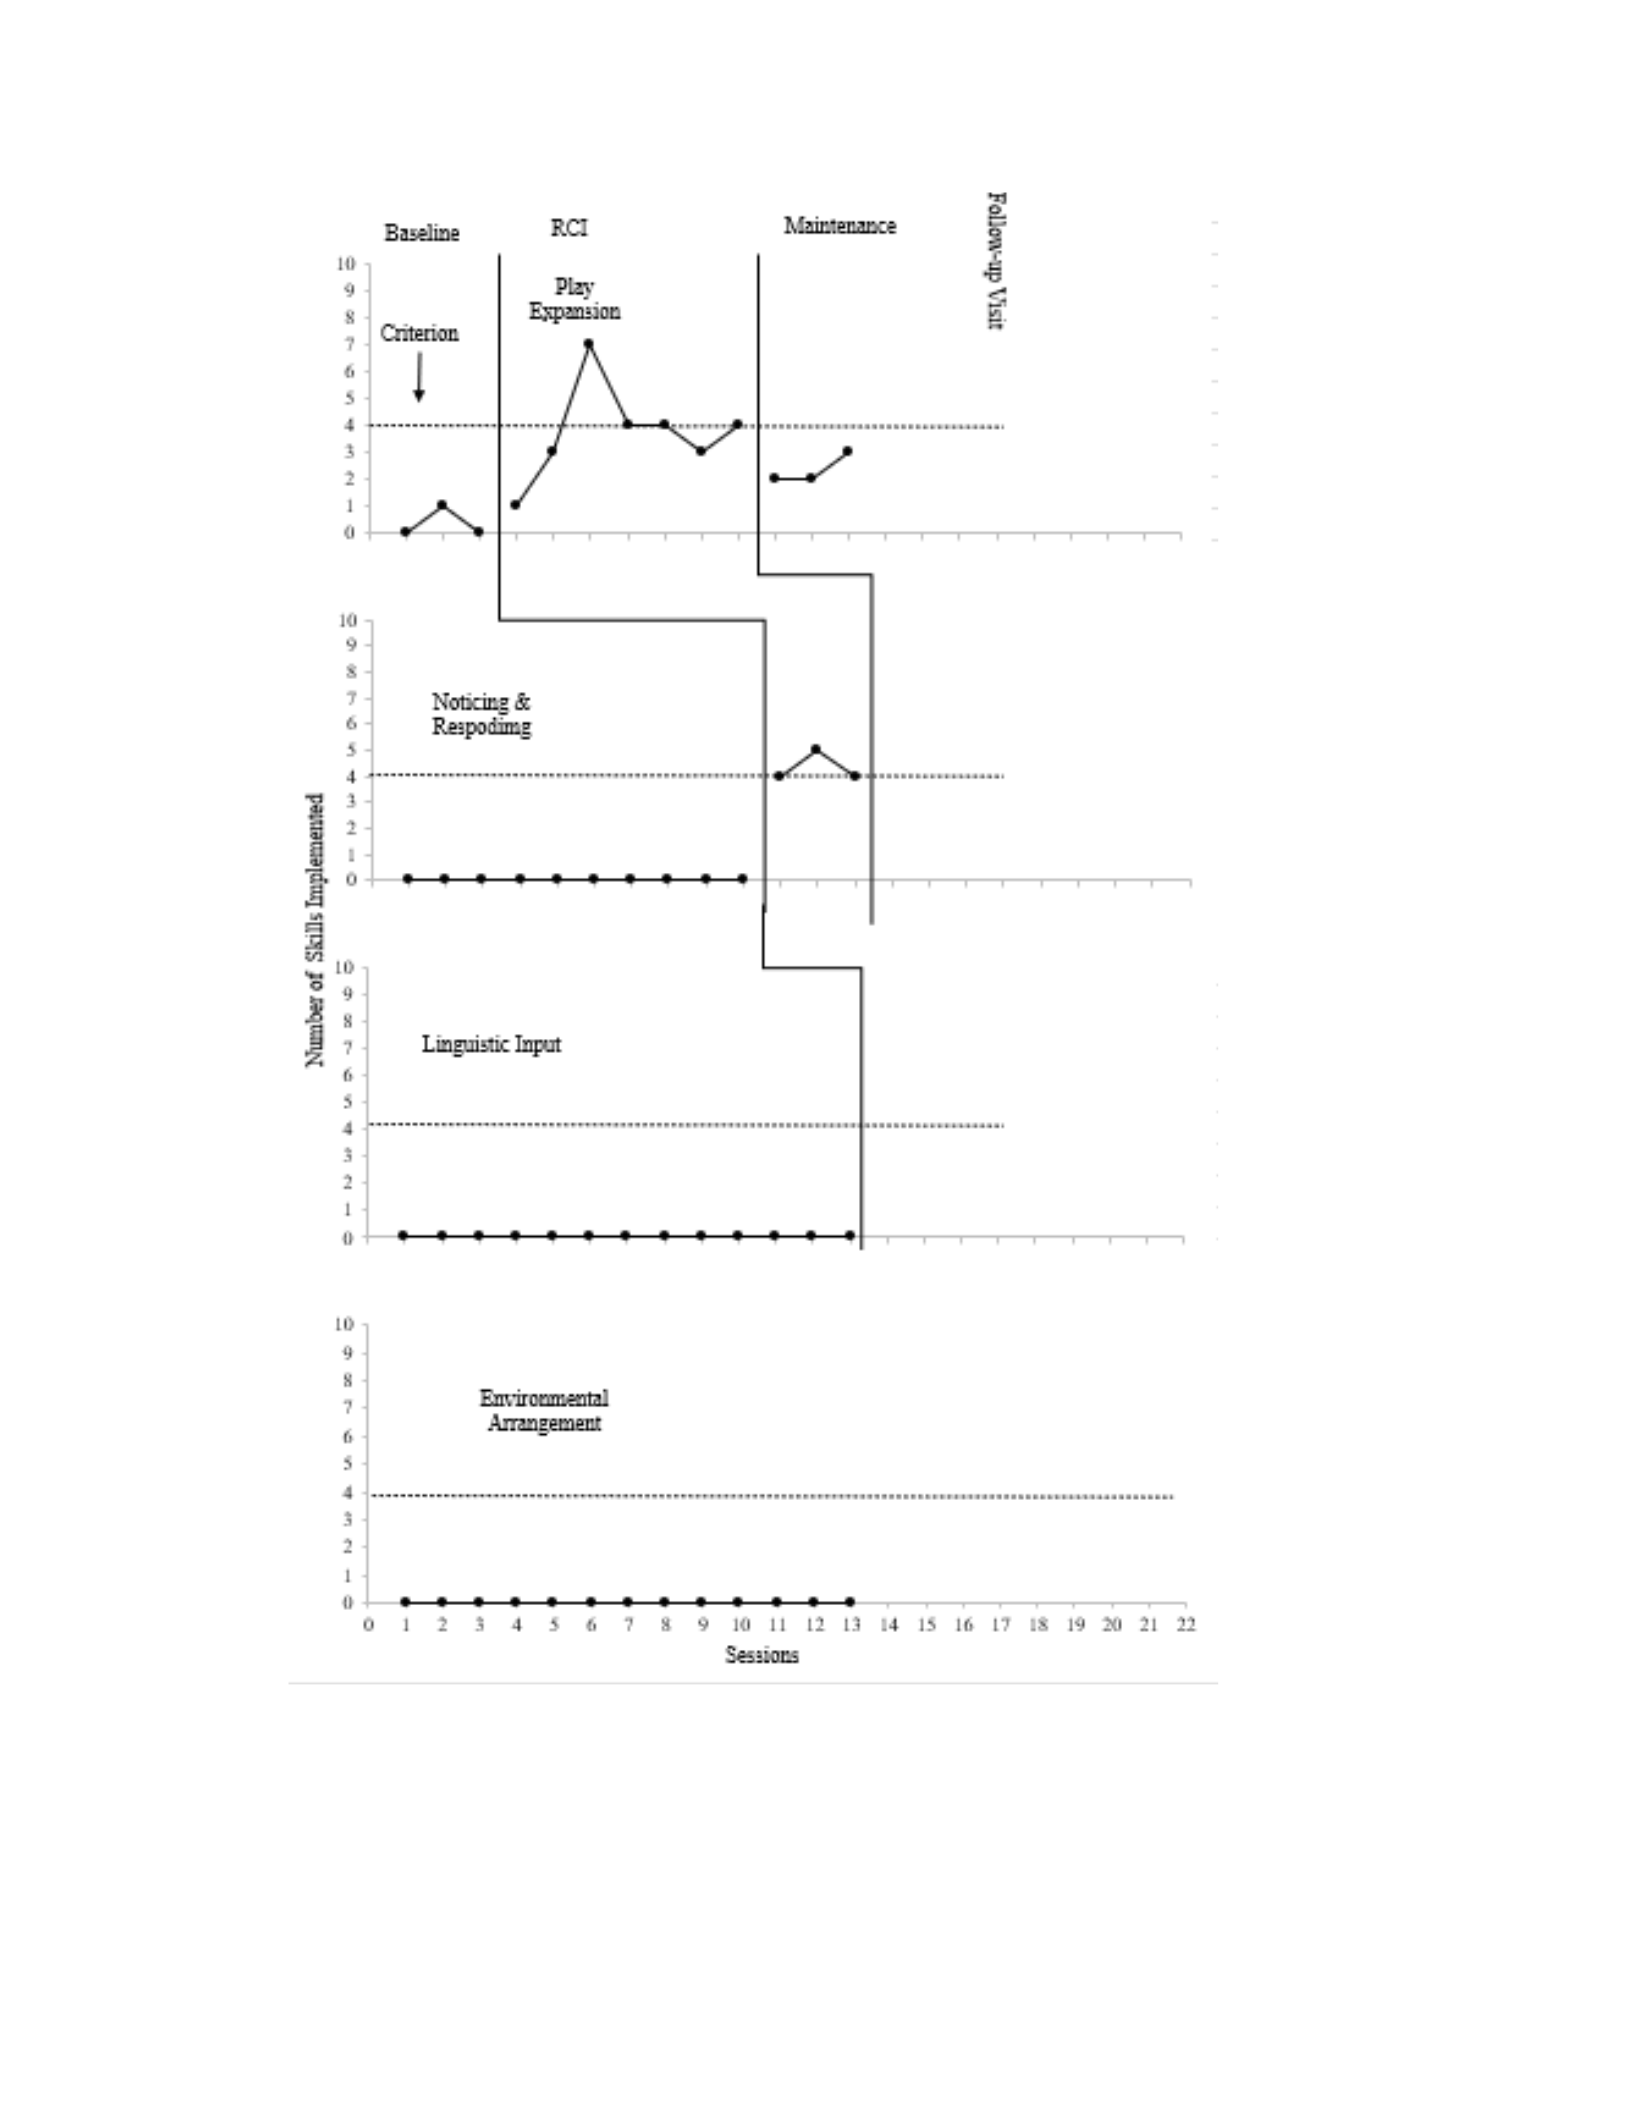
Caregiver Use of Naturalistic Strategies
The results of caregiver skills throughout the study are presented in Figure 1 and
will be visually analyzed across all conditions. During the baseline condition, the parent
only engaged in play expansion (Tier 1) once (across three sessions) before the training
and coaching sessions. Analysis of the baseline data path demonstrated a low level of
responding with a stable trend and low levels of variability. Data paths for all other tiers
(2-4) were all stable, indicating a low level of responding with a zero-celerating trend and
no variability in data. Since there were low levels of responding and stability across all
tiers, the intervention for Tier 1 was introduced.
After introducing the intervention in Tier 1, improvements in play expansion were
observed across the data path. The first datapoint intervention condition overlapped with
the highest point along the ordinate in the baseline condition. For the second and third
intervention sessions, an accelerating trend in a therapeutic direction was observed in the
data path. During the four subsequent sessions the data were relatively stable at or near

28
the criterion. Because the caregiver met the criterion during Intervention Session 5, we
considered this a basic demonstration of effect. Additional sessions were conducted
during that visit because of the time scheduled with the family and because data are
coded after visits. In addition, if we were collecting data live, we would have
discontinued the remainder of the visit because the caregiver met the criterion. Thus, a
basic demonstration of the effect was evident for play expansion. The caregiver
coordinated play expansions when receiving the intervention in Tier 2. Still, data were
lower when compared to the intervention condition, but at a higher level relative to
performance in the baseline condition. Data remained stable in all untreated tiers.
The intervention was introduced in Tier 2, and an immediate and abrupt change in
level was observed in the data path. Caregiver data were stable along the ordinate with a
range of 4-5 occurrences, and no overlap between the baseline and intervention condition.
There was no identifiable trend in the data path in the intervention condition. A basic
demonstration of effect was displayed for the second target behavior of noticing and
responding to the child’s communication. Baseline data in Tier 3 and Tier 4 remained
stable, occurring at a low level along the ordinate with a zero-celerating trend in the data
paths. The intervention will be introduced in Tier 3 beginning on April 8th, 2024.
Because only two basic demonstrations of effect at two different points in time have been
observed in the data path, I cannot determine if a functional relation is present at this
time.
29
Figure 1 Caregiver Behavior
Child Behavior
Child Communication
30
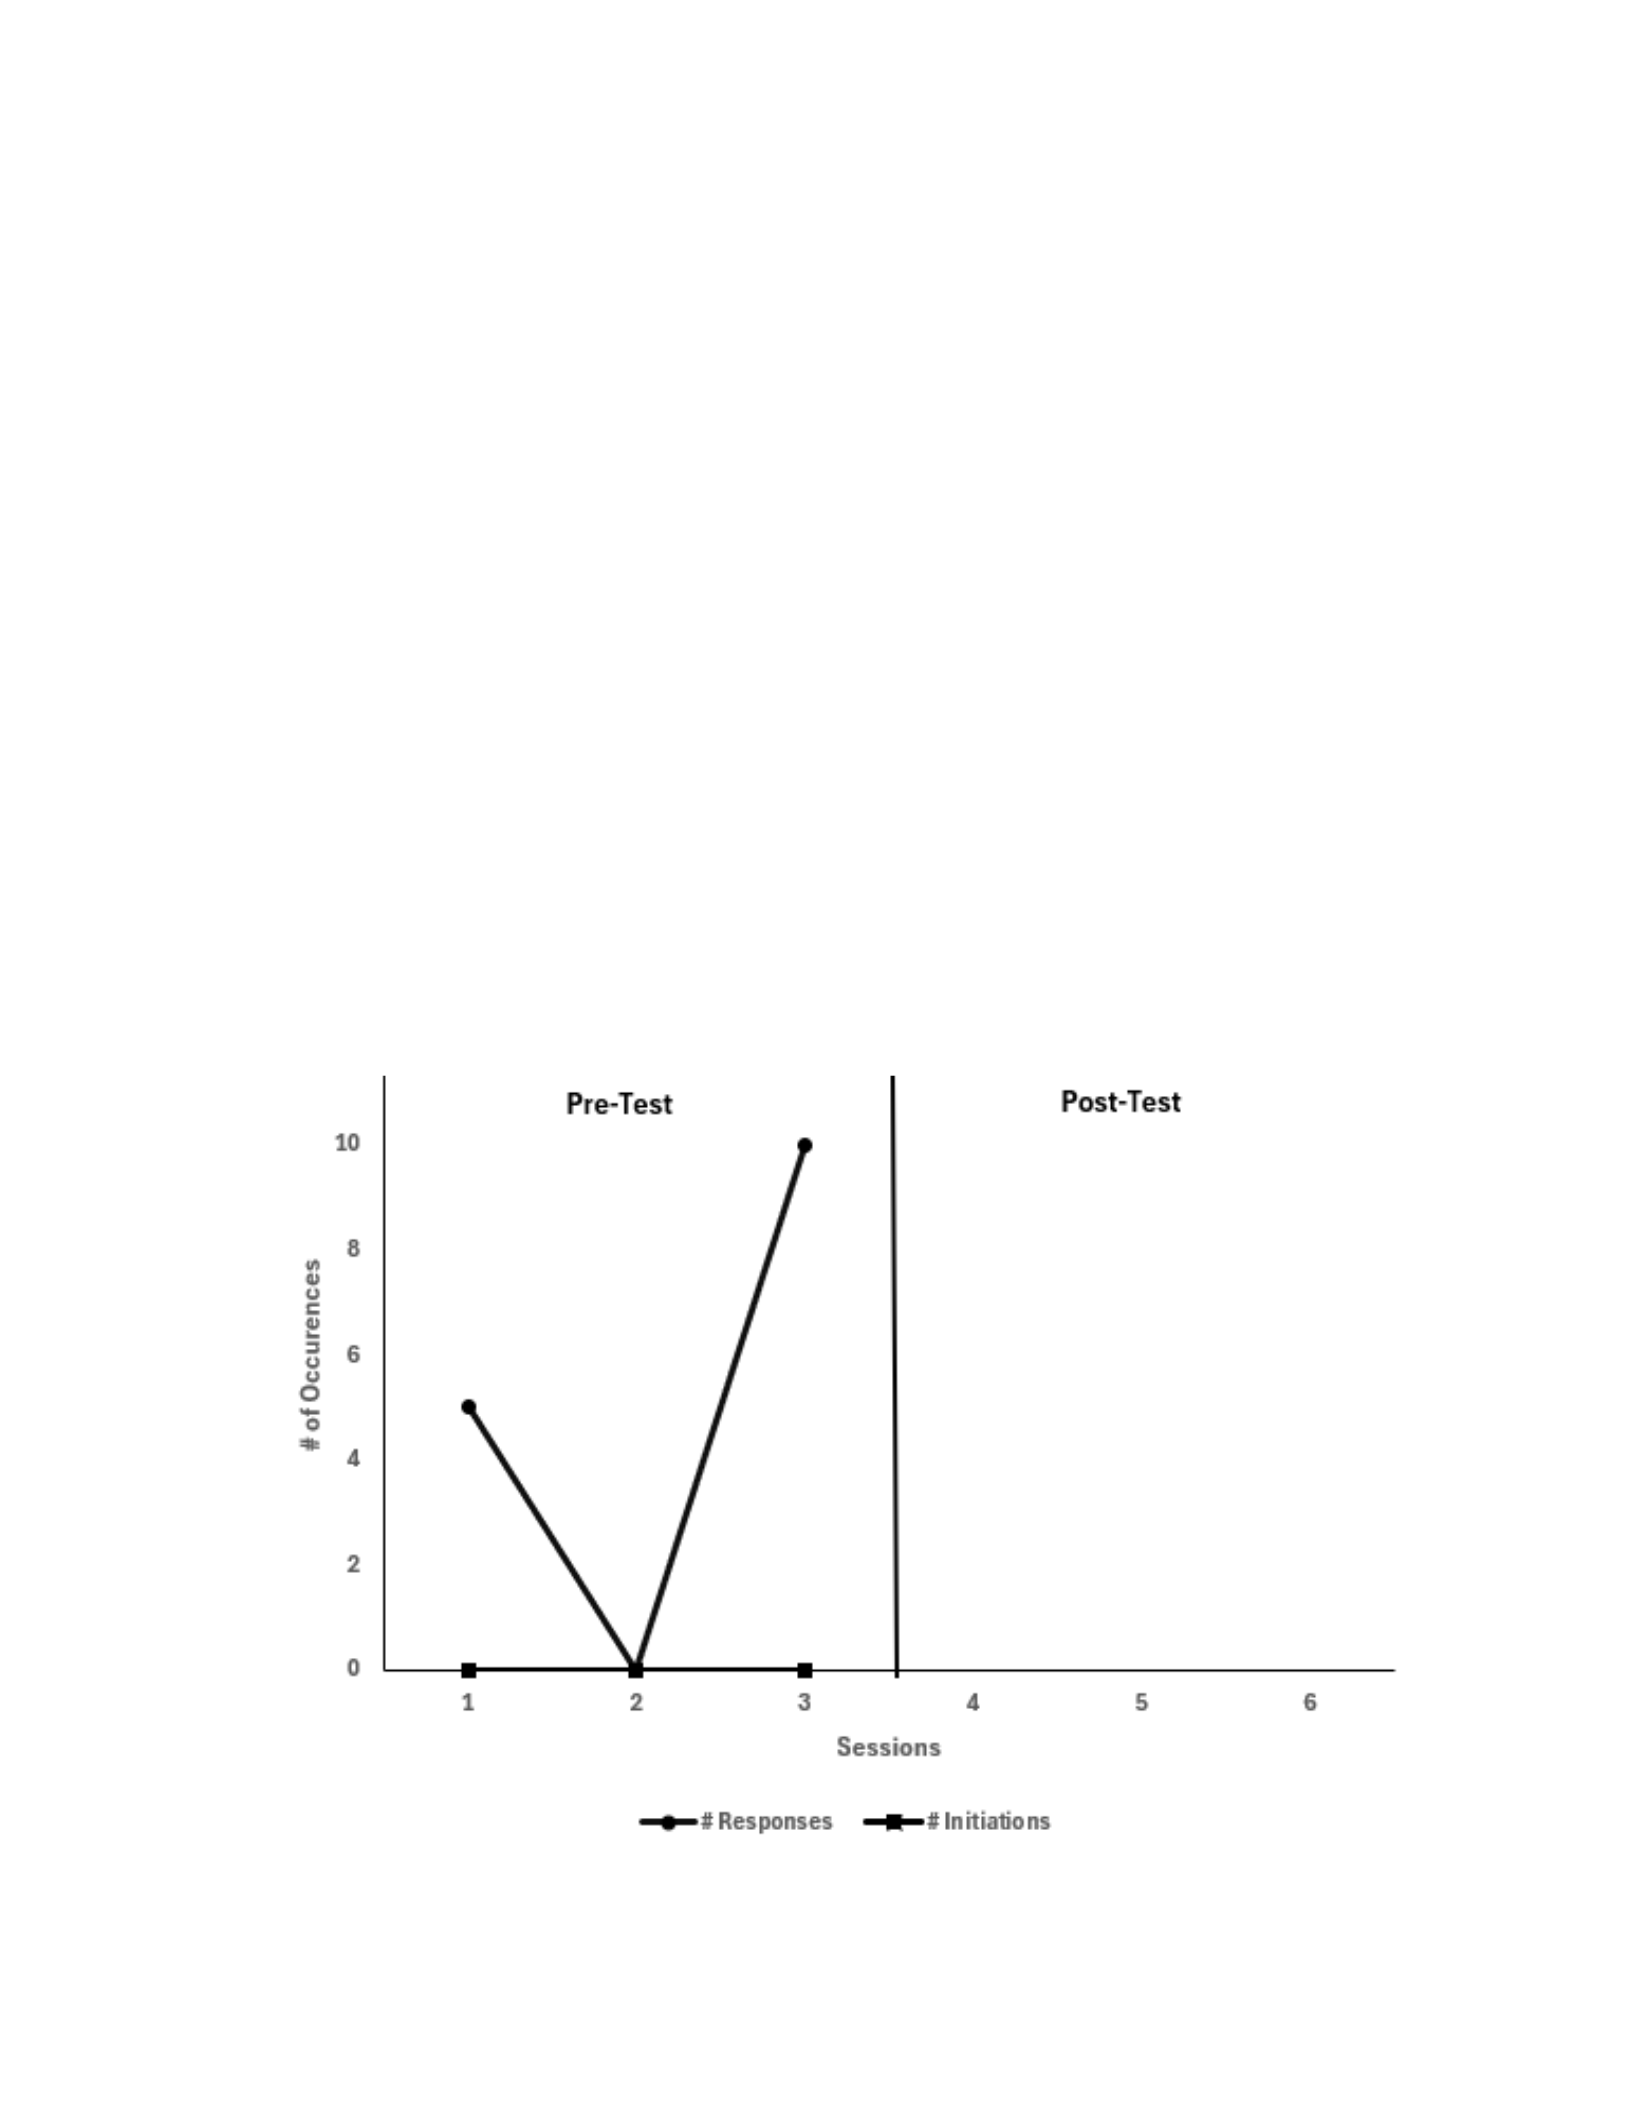
The results of child communication behaviors during the baseline condition are
presented in Figure 2 and will be visually analyzed across a pre and post-test condition.
Baseline or pre-test results for child communication behaviors indicated highly variable
levels of responding, ranging from 0-10 responses per session (4 min). There was no
clear trend or level in child responding due to the high level of variability. There were no
instances of the child engaging in spontaneous initiations during the pre-test sessions.
Therefore, data indicate a low and stable level of spontaneous initiations, with a zero-
celerating trend in the data path. At this time, formal data collection for the post-test on
child communication behaviors has not yet occurred. Data analysis will occur and be
evaluated across and within pre- and post-intervention conditions. Data collection for
child communication behaviors is in progress, with an anticipated end-date of mid-May
2024.

31
Figure 2 Child Communication Behaviors
Child Happiness
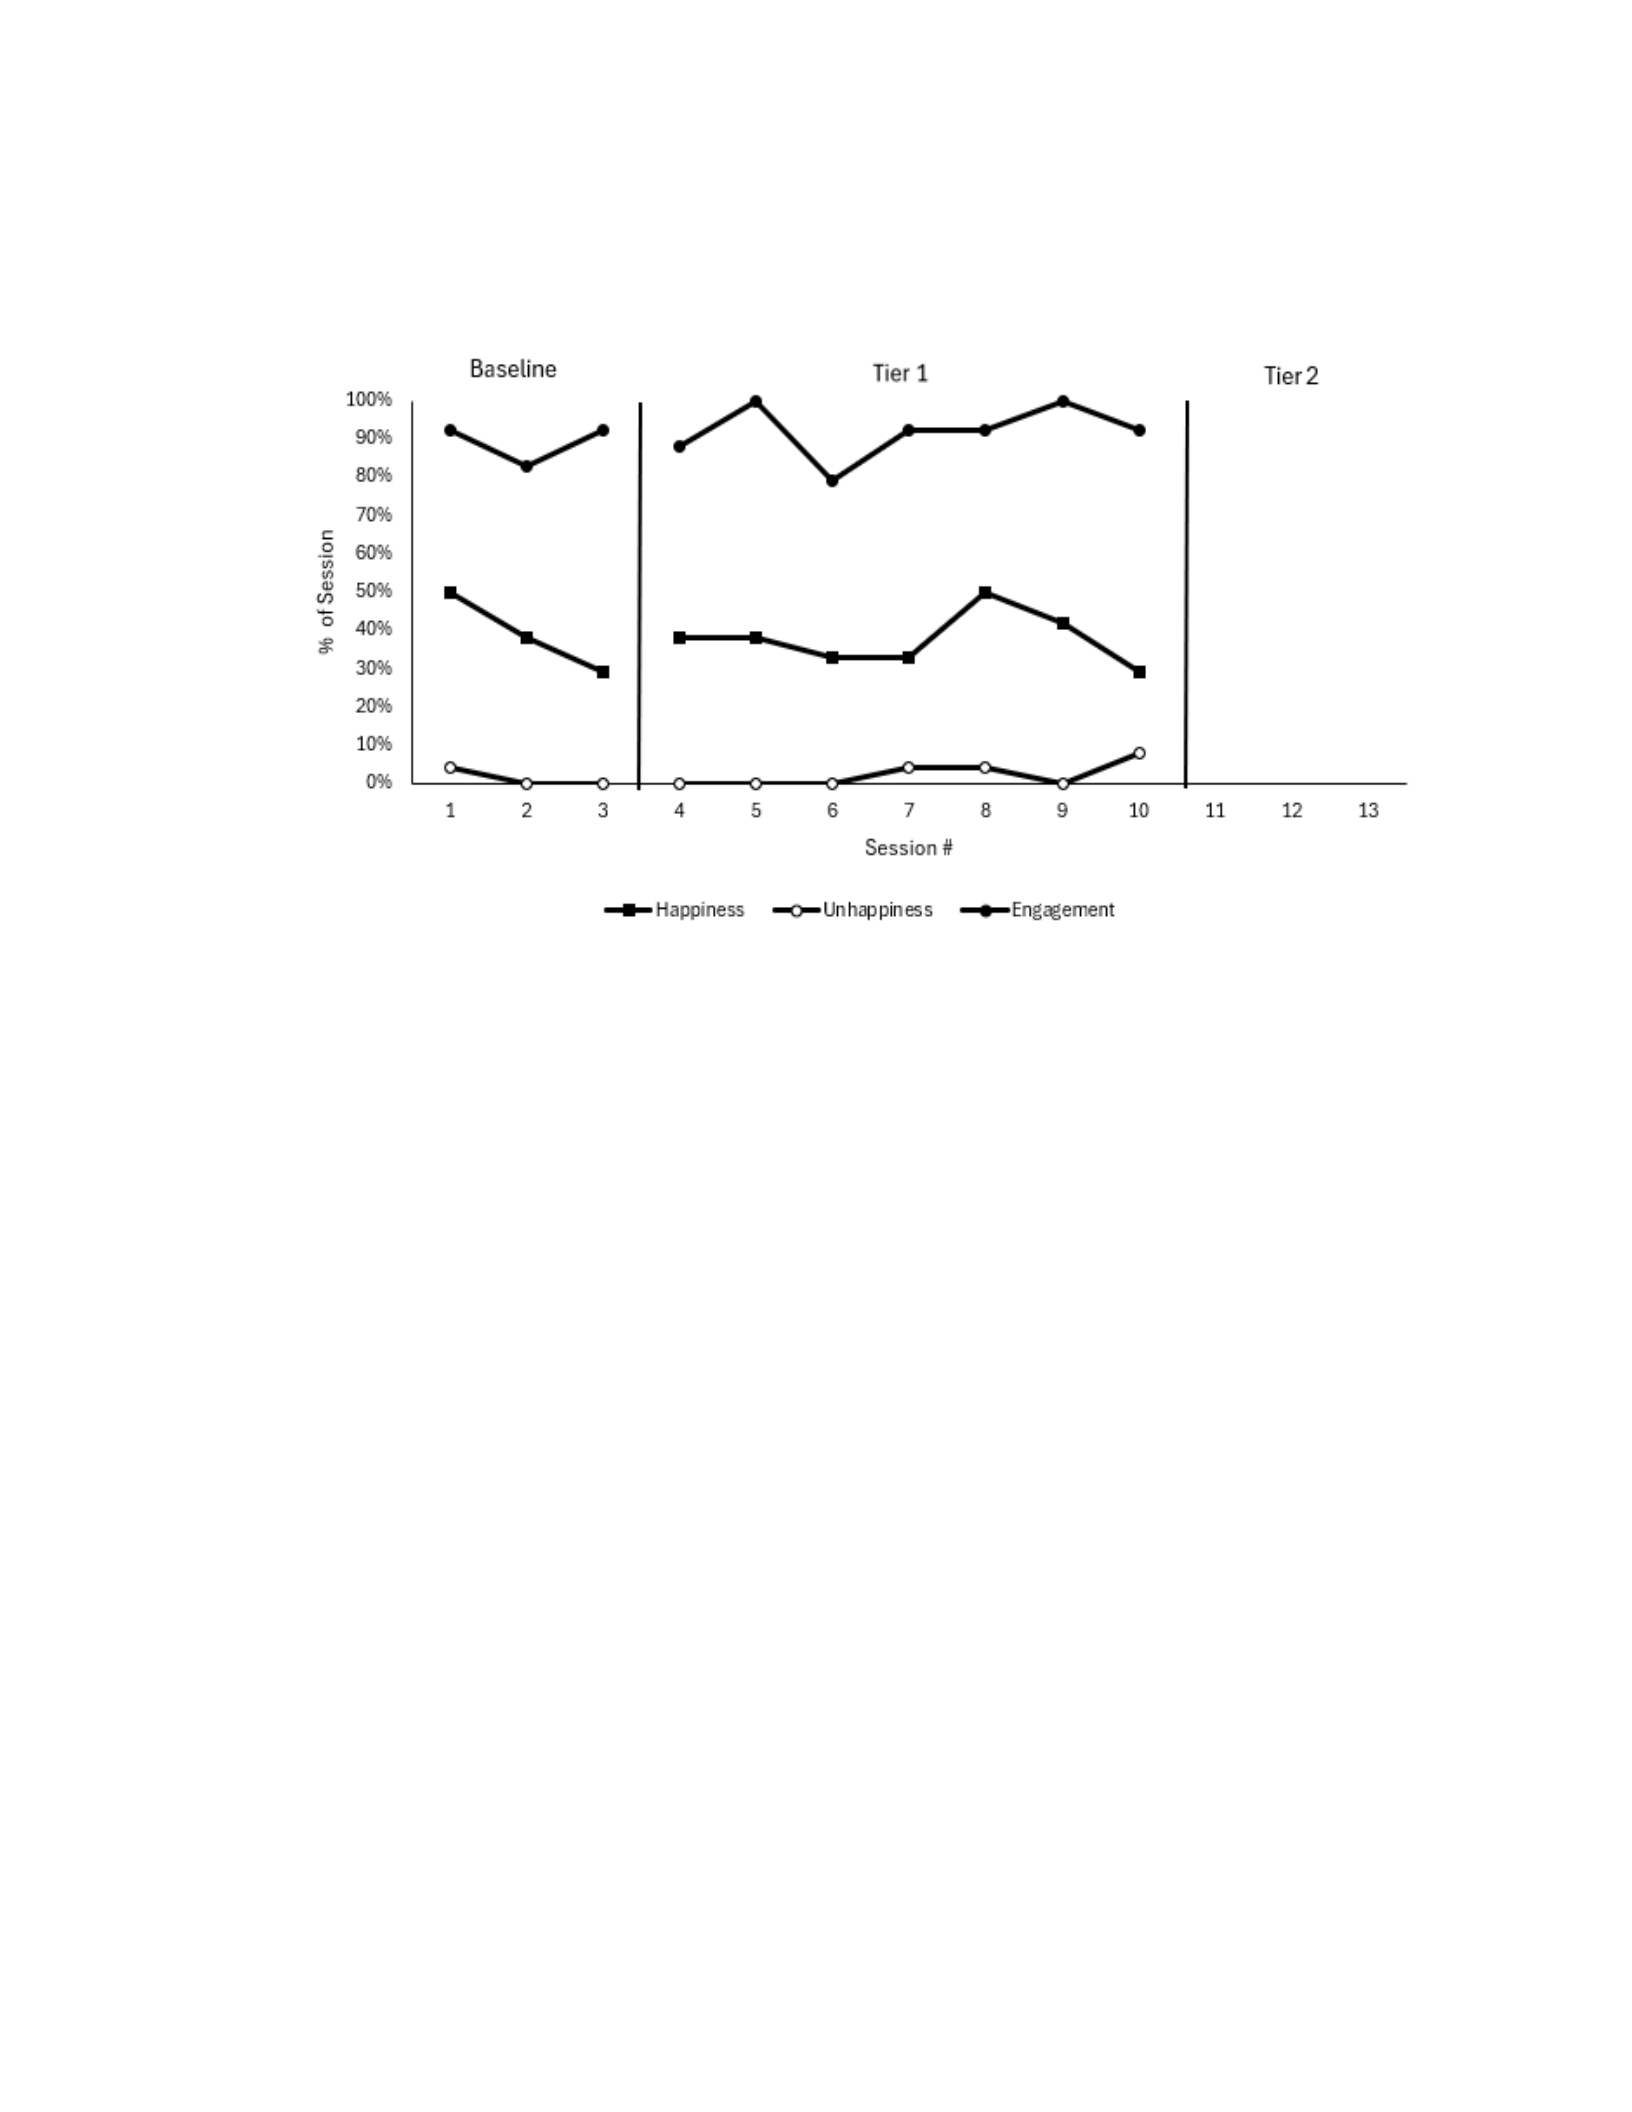
The results of child happiness behaviors are presented in Figure 3 and were
visually analyzed across baseline and intervention conditions. Overall, data have
remained relatively stable across conditions. Baseline-level results for child happiness
behaviors indicated slightly variable levels of responding, with a range of 29-50% along
the ordinate and a median value of 38%. During baseline sessions, there was a moderate
level of response and a decelerating trend in happiness behaviors. Variables related to
happiness behaviors included unhappiness behaviors and joint engagement with the
caregiver. Baseline results for child engagement indicated stable and high levels of
responding, with a range of 92-83% along the ordinate and a median value of 92%. There
was also a zero-celerating trend for engagement during baseline sessions. Baseline results
for child unhappiness behaviors indicated stable and very low levels of responding with a
range of 0-4% along the ordinate, and a median value of 0%. There was a zero-celerating
trend for unhappiness behaviors during baseline sessions.
Following the introduction of the intervention, there was no immediate effect on
child happiness. During intervention (Tier 1), child happiness was at a relatively
moderate but variable response level, ranging from 29-50% along the ordinate and a
median value of 38%. Child happiness did not have a clear trend during the intervention
condition. Intervention results for joint engagement indicated stable and high levels of
responding, with a range of 79-100% along the ordinate and a median value of 92%.
Intervention results for child unhappiness behaviors reflected stable and low levels of
responding a range of 0-8% along the ordinate and a median value of 0%. At this time,
formal data collection for happiness behaviors has only been completed for sessions 4-10
32
or Tier 1 of the intervention. Data coding and analysis for additional tiers will be
completed as the project progresses.
Figure 3 Child Happiness and Engagement

33
Discussion
The goal of this study was to replicate and expand the results of Lane et al. (2016)
by evaluating the proposed RCI with a caregiver with a young child with a disability, as
well as to investigate child happiness as a proxy for social validity of the intervention for
the child. The intervention was a multi-component, rapid coaching intervention, which
included an interventionist providing a caregiver with rationales, modeling opportunities,
coaching throughout brief sessions, and performance-based feedback. The caregiver was
trained and coached on naturalistic strategies associated with improved expressive
communication in young children with disabilities who display difficulties verbally
communicating with others. It is important to note that although the caregiver did not
display target behaviors during baseline conditions, she was actively engaged with her
child throughout all sessions. During baseline, the caregiver did not display the target
skills, rather, caregiver play included asking multiple questions (e.g., “Do you want to
play with me? What are you doing? Are you building a tower? etc.), singing, and
imitating her child’s play. Thus far, the intervention has led to improvements in two
caregiver behaviors, with no changes observed in untreated tiers until the intervention
was introduced. The caregiver was taught to expand her child’s play behaviors and to
notice and respond to her child’s communication during play-based activities. Thus far,
only one coaching prompt was needed for the caregiver during training sessions (e.g.,
researcher tells the parent, “Now would be a great time to expand on the play”). Next, the
caregiver will be taught how to provide linguistic input (narrate her and her child’s play)
and arrange the environment to provide her child with opportunities to communicate.
Limitations

34
There were numerous limitations within this study that should be addressed. The
first limitation of this study is that the study is ongoing. The extent to which this study
replicates findings in previous studies will remain unknown until the study is complete.
Improvements in two caregiver behaviors are promising, but no formal conclusions can
be made regarding the presence or absence of a functional relation. Additionally, child-
level data coding is not complete. Child communication data has not been coded or
evaluated for the post-test condition, and child happiness has not been coded or evaluated
for Tier 2. Once all training tiers and data collection have been completed, the results and
implications of the study may be more significant.
The second limitation of this study was that results were based on the
performance of one caregiver, allowing for only potential intra-participant replication.
Thus, there was no inter-participant replication within this study. Another limitation was
that the caregiver’s generalization was not formally assessed. The caregiver verbally
reported that she was practicing the strategies frequently with her child outside of
coaching sessions. Further, social validity data have not been collected because the study
is ongoing. However, the caregiver verbally reported that since beginning the training,
she felt that her child was more willing to communicate and engage in play activities with
her.
An additional limitation was conducting online sessions but formally coding data
after the meeting with the caregiver. For example, as evidenced in Tier 1, the caregiver
reached the criterion in Tier 1. Still, additional sessions within the same visit were
conducted, with one of those additional sessions below the criterion (i.e., 3 occurrences
instead of 4). Second, monitoring child behavior was especially difficult using the

35
online/recorded video format. Although the caregiver tried to stay in the camera frame,
there were times that the child moved away from the camera or was at an angle where it
was difficult to see either one or both participants (e.g., standing directly in front of the
camera with only torso visible, sitting/laying parallel or perpendicular to the camera,
etc.). This made coding happiness particularly difficult and caused the coding to be less
sensitive to some behaviors. For example, one of the main happiness behaviors for the
child was smiling, but there were many times when his face was off-camera completely
or obscured by the angle he was facing. Thus, some happiness/unhappiness behaviors are
likely under-represented in the data due to an inability to code some behaviors that
potentially occurred off-camera. Future researchers should ensure they use various
happiness behaviors, especially auditory behaviors that can be recorded on or off-camera
(e.g., laughter).
Implications
The caregiver was taught naturalistic strategies, which were selected because they
are commonly recommended for promoting early communication and language
development in children (Schreibman et al., 2015). Teaching naturalistic strategies to
caregivers has potential benefits over professional-only implemented interventions since
families typically spend the most time with the children (i.e., outside of professional
service settings). If implemented at fidelity and recommended dosages (Bailey, 2024;
Lane et al., 2024; Warren et al., 2007), training caregivers to implement these strategies
can be a time- and cost-effective strategy that can potentially benefit all involved parties.
Since replicating the RCI using an online format was successful, there are
practical implications for practitioners providing online services or with large caseloads.

36
Families in rural or underserved areas may be more easily able to access services such as
the RCI if they are offered online or remotely. Additionally, training families via video in
their natural environment may be useful for generalization purposes (e.g., practice using
their own toys/space) and be less intrusive than home-based sessions (this is dependent
on family preferences). The results of this study add to existing literature on naturalistic
strategies by demonstrating an online intervention that involves a team of people (i.e.,
different professionals and family members) collaborating to support a child’s acquisition
and generalization of language skills.
Previous caregiver training literature has not included a measure of child
happiness to evaluate the social validity of these interventions. Given the history of
psychology and applied behavior analysis (Bailey & Burch, 2019; Kirkman, 2017;
Perone, et al., 2023), it is crucial that researchers and practitioners take the thoughts and
feelings of their clients into consideration, especially when working with vulnerable
populations such as those with disabilities or communication delays. Practitioners should
consider the utility of including an assessment of happiness during interventions to assess
social validity, especially when participants have limited vocal repertoires. Across all
conditions, the interventionist asked the caregiver to describe the child’s temperament or
mood that day. Although this information was not formally evaluated, this narrative
information informed our analysis of happiness behaviors and could have potentially
explained potential variabilities if data were variable. Future researchers should consider
methods of assessing happiness behavior and possibly ask the caregiver if the indices of
happiness and unhappiness are representative of their child’s most common behaviors.

37
Throughout this study, a new component was added to the procedures to tailor the
coaching sessions to the caregiver by asking their feedback and training preferences. By
individualizing the coaching sessions to include this feedback, we found anecdotal
evidence that some families may want different levels of feedback and modeling. For
example, previous iterations of the RCI required the interventionist to show the caregiver
a recording of their implementation with their performance feedback, however, in this
study the caregiver did not wish to review any recordings of her sessions.
Individualization of training and coaching procedures may also help improve buy-in from
caregivers by increasing rapport and their level of control in the process. This may also
empower the caregivers we train to provide us with helpful feedback on the training
process. Future research should consider formally evaluating using the tailored version of
the RCI protocol.
Additionally, this research included previous studies (Cambell 2022; Reiss 2023),
which focused on improving and adding to the literature on interdisciplinary
collaboration between SLP’s and behavior interventionists. Interdisciplinary collaboration
helps focus all adult efforts on teaching important skills across developmental areas and
is crucial for a child’s developmental trajectory (Ronfeldt et al., 2015). This study
contributes to the interdisciplinary literature by modeling a successful collaboration
between a SLP and a behavior interventionist to train caregivers on strategies to promote
expressive communication in their child. Currently, formal data collection of child
communication behaviors is in progress. Communication data will be utilized to analyze
relations between the caregiver’s use of naturalistic strategies and concurrent child
communication (in responses and spontaneous initiations). This data will be collected and

38
analyzed before, during, and after the collaboration and coaching occurred, to see if there
was any change in the child’s expressive communication.
Conclusion
The purpose of this study was to evaluate the effectiveness of a tailored RCI (training and
coaching) with caregivers of children with developmental disabilities. This study
replicated Lane et al. (2016) and included components from other studies (e.g., Campbell,
2022) and recommendations (Gullet, 2024; Lane, 2023). Additional data are needed to
determine the effectiveness of the tailored RCI for teaching a caregiver to implement
naturalistic language strategies during play. Additional data is also needed to determine
the effect of collaboration and RCI on child communication and happiness behaviors.
This study extends previous literature on caregiver coaching by evaluating child-level
happiness to assess the social validity of caregiver coaching interventions. This can
potentially serve as a model for future research on conducting caregiver coaching that
includes evaluation of child happiness and social validity. It is recommended that future
researchers continue to explore the effects of the RCI and how to accurately and
meaningfully collect social validity data from participants with limited or no verbal
repertoires.

