


Findings on Nurse Education and transition to practice: radical transformation
This paper reports on three major themes that emerged from this study - “under prepared for
practice”, “overwhelmed & abandoned” and “need for clinical supervision”. These findings
were interpreted within a risk management framework (Benner, 1984; Johnstone & Kanitsaki,
2006; TeamSTEPPS Instructor Guide, 2006) and had patient safety implications. The
participant’s comments illustrate their concerns.
Underprepared for practice
This theme was present throughout the focus group discussions illustrated by the NGRN’s
struggle with transferring theory into practice (Ostini & Bonner, 2012). The following challenges
were identified with regard to preparation as an undergraduate:
• Expectations of the role of student were much different to that of registered nurse.
• Prioritization of care was difficult to practice.
• Participants reported that on clinical practicum they were able to focus on individual
tasks and with an ideal number of patients/clients. Opportunity to provide total patient
care to a larger number of clients, and all of the other aspects of the registered nurse role
was not provided.
Other aspects of the role includes multitasking, for example, answering the telephone,
addressing security incidents, managing patient safety incidents, attending accident & emergency
all at the same time and meanwhile being responsible for prioritizing the care for a group of
patients on the ward.
When you trained in a city hospital a third year student has to take four patients…I’ve
had fifteen…with an EN, dealing with outpatients and the phone and everything. (JA)
Participants reported that as students on clinical practicum they rarely had the opportunity to
practice the role of team leader, yet this was a frequently reported expectation, very early in the
first year of practice. They also found that organization of the interdisciplinary team was part of the
new graduate role. As a consequence, new graduates reported the need to develop skills to have
a whole of health service perspective in unpredictable environments:
That’s the same …I’ve had a shift …well…many a shift where I’ve been Team Leader…one
classic example was...we always have an RN on…she got called to the labour ward….we
had a girl in labour…then we had a woman come in who had to be sectioned…so I had to
organize a team to come in to do the section…so it was just the EN and I…for a ward full
of twelve or thirteen patients. (AL)
The above is an example of how a new graduate was required to prioritize patient care and contact the
‘on call’ team for the operating room so that a caesarian section could be performed. The skill

of adaptability, leadership, situational awareness and the ability to work independently was
required (Ostini & Bonner, 2012). Situational awareness requires timely and expert clinical skills to
assess the relative acuity of each patient and adjust priorities in accordance with the human and
material resources available. These skills are essential to ensure patient safety. Where support
with development of situational awareness is lacking the NGRN’s would feel overwhelmed and
abandoned.
Overwhelmed and abandoned
In the focus groups NGRN’s reported that they were expected to work on their own or ‘step it up’
at a very early stage in their practice, which could be as early as two months after registration as a
nurse. It was also reported that promises such as preceptorship, workplace orientation, feedback
and other support strategies did not eventuate (Lea & Cruickshank, 2005). The leadership support
issues were identified and include the following:
• Orientation to the health unit did not occur
• The new graduate registered nurse often had to work alone.
• There were systems failures such as having an unreliable “on-call” procedure.
• Preceptors were not prepared for their role or did not fulfill their role.
• Little feedback on performance was provided.
• Systems were not in place to facilitate the preceptor role. For example, the NGRN
and preceptor were not allocated shifts where they could work together or debrief.
• There was abandonment reported in an inter-professional context.
The following three scenarios provide evidence of the leadership support issues:
Scenario 1
The NGRN is not only working alone, but also finds that nurses designated to be “on call” were not
accessible when contact was attempted. In this instance the network of support has diminished.
There needs to be an “on-call”… a name and a number for weekend “on-call” at all times, I
have rung that number, fortunately not for an emergency… and “sorry didn’t get your
phone call, when did you ring me?” Two hours ago! Glad I didn’t need you in a hurry
because I haven’t got any other RN in the building with me. I’d like to be more confident
that firstly, I had an “on-call,” and second the “on-call” was available at all times. (FR)
Scenario 2
The NGRN is not able to work with the preceptor as the staff allocation processes are not in place for
this to occur. Here it is also evident that novices are working together instead of with more
experienced nurses, hence errors or omissions may be overlooked which limit safe patient care.

I have had very little if any, in fact zero contact with my preceptor, because she’s too busy
doing what she’s doing in her role. And just short staffed…and so I’m not criticizing the
person….she’s a world of knowledge but just physically hasn’t had the time to come and
see, in passing she’d ask if I was going Ok. But I think you need to be put on shifts with
that person and that person needs to have some experience not just a graduate. (TA)
Scenario 3
The following scenario illustrates that effective interprofessional relationships are essential to
ensure patient safety. This experience was reported as traumatic and the new graduate reported
problems coping with these memories when later confronted with patients who presented with
similar circumstances surrounding their admission.
And there happened to be another doctor walking in the ward at that time and I said “could you
come and see this patient for me I need help! …and he did not realize the significance of it at
the time and he said “ No I can’t”….because of the system and how it is… you need
to get the duty doctor and it wasn’t his patient and well the man was arresting…the doctor
actually looked in and said this man is arresting…the whole experience afterwards … I felt
like the whole world was on my shoulders and I cried… because I tried to get someone [a
doctor] who I thought would help me but then NO that didn’t happen… (JN)
Need for Clinical Supervision
New graduates expressed the need to learn about quality and safety in clinical practice
(Johnstone, Kanitsaki, & Smith, 2004; Johnstone & Kanitsaki, 2006; Spector, 2011) from
the beginning of their careers:
• They were keen to adopt evidence-based practice and have guidance while they
developed as a professional nurse.
I’d rather be told I’m doing something wrong and know that that’s not the way to do it…this
is how you should do it, rather than keep on doing something the wrong way…and then
someone just goes off at you one day because you’ve been doing something wrong for six
months. (LE)
• Others expressed concern, that they were placed in situations that required skills
beyond their level of education and experience. The NGRN in this scenario, when
stating “not having really any clue what I was doing”, is also working outside of her
scope of practice and has no apparent voice to alter the situation.
I’d be looking after high dependency patients and [a lot of emotion here] just not having
really any clue what I was doing and like just managing to get through without killing
people… that’s what I kept thinking at the end of the shift. “I didn’t kill anyone today...it’s
been a good day let’s get through it. (MA)
• NGRN’s stated that they do not possess the skills or experience to practice without
supervision at such an early stage of their nursing career. There is a high level of
anxiety about making serious errors in clinical practice. The NGRN’s were keen to have
experienced registered nurses work alongside them and were frustrated that this did not
happen as promised.

How can they support you and give valuable feedback if they don’t work with you, you could
go through the whole year and develop bad practices and just flounder your way through,
but if you have got a good preceptor they can actually point out...this is something you
might need to work on…and they are not going to get that from sitting in their office. (JE)
Discussion
NGRN’s reported that they were underprepared for the realities of clinical practice. Workload
demands and decision-making requirements changed dramatically after registration and NGRN’s
did not consider themselves to be workplace ready, confident and competent. It was an
expectation of managers that NGRN’s would be left in charge of a ward or department and in
some instances the entire hospital with just an “on call” number to ring. Leadership support is
required for the NGRN’s during transition to professional practice. Hence, the first core element
identified is the need for purposeful leadership that entails the provision of a network of support
(Lea & Cruickshank, 2007; Spector, 2011) to both scaffold the new graduate and ensure safe
patient care.
Abandonment of the NGRN was apparent with little evidence of support networks. Coping without
a preceptor, and little feedback on practice, is fraught with danger because the NGRN that is
unsupervised adopts “trial and error” as a means to cope (Spector, 2011). There is evidence that
NGRN’s have continued to practice unsafely for long periods (Orsolini-Hain & Malone, 2007;
Spector, 2011) because there was no guidance provided. In a previous study (Bjørk & Kirkevold,
1999), four nurses were followed for up to 14 months as they performed dressing changes on
new post- operative surgical patients. The nurses reported that they had improved their skills and
were now more confident and competent. However, analysis of their practice showed no
difference in outcomes for the patient throughout the study period. For example, wounds were still
being contaminated and wound drains unsafely removed.
Patient’s lives may be lost unnecessarily because the NGRN is unable to identify pre-arrest or
failure-to-rescue scenarios (Ashcraft, 2004). According to Kolb (1984) when adopting a new role
the novice (new graduate registered nurse) has the challenge of relating theory to practice
through active experimentation. This involves processing previous learning through reflection,
adding new knowledge from experience, integrating this into pre-existing concepts and make
sense of the experience (Kolb, 1984). The intensive process of interpreting and contextualizing
knowledge makes the NGRN vulnerable. Oversight of the NGRN during the early stages of
practice development by an expert nurse, one who has the capacity to anticipate and act in the
event of possible complications, reduces the likelihood of adverse outcomes for patients (Ashcraft,
2004; Thompson & Yang, 2009).
Supervision of the novice nurse by an experienced nurse is therefore critical to ensure safe
effective care. Internationally, there is evidence that, when formally implemented, preceptorship
programs, are successful in facilitating the transition of new graduate nurses (Dracup & Bryan-
Brown, 2004; Greenwood, 2000; Lea & Cruickshank, 2007; Spector & Echternacht, 2010b)
The potential to “fail to intervene” is significant when the new person is unsupported, stressed and
uncertain. Stress and anxiety alone can compromise the NGRN’s decision-making (Benner, 2004b; Lea
& Cruickshank, 2007; Spector, 2011; Spivak, Smith, & Logsdon, 2011). It is customarily believed that
the novice/advanced beginner will know when to get assistance when a patient deteriorates however
this is not supported by the evidence (Ashcraft, 2004). In this study, the findings also provided evidence
that there was uncertainty, apprehension and misunderstanding with regard to role relationships.
Relationships with medical staff were not clearly defined and there was a need to facilitate an inter-
professional culture of support (Schoesler & Waldo, 2006)
Developing inter-professional support networks is essential to building capacity in the new
graduate. Relationship development will also facilitate situational awareness, patient advocacy
and comprehensive care planning in a collaborative context (Dougherty & Larson, 2005; Spivak, et
al., 2011; Weller, Barrow, & Gasquoine, 2011)
Nurse-physician collaboration is a key factor in nurse job satisfaction, retention, and job
valuation. Decreased risk -adjusted mortality and length of stay, fewer negative patient
outcomes, and enhanced patient satisfaction have also been associated with better
nurse-physician collaboration. (Dougherty & Larson, 2005, p. 244)
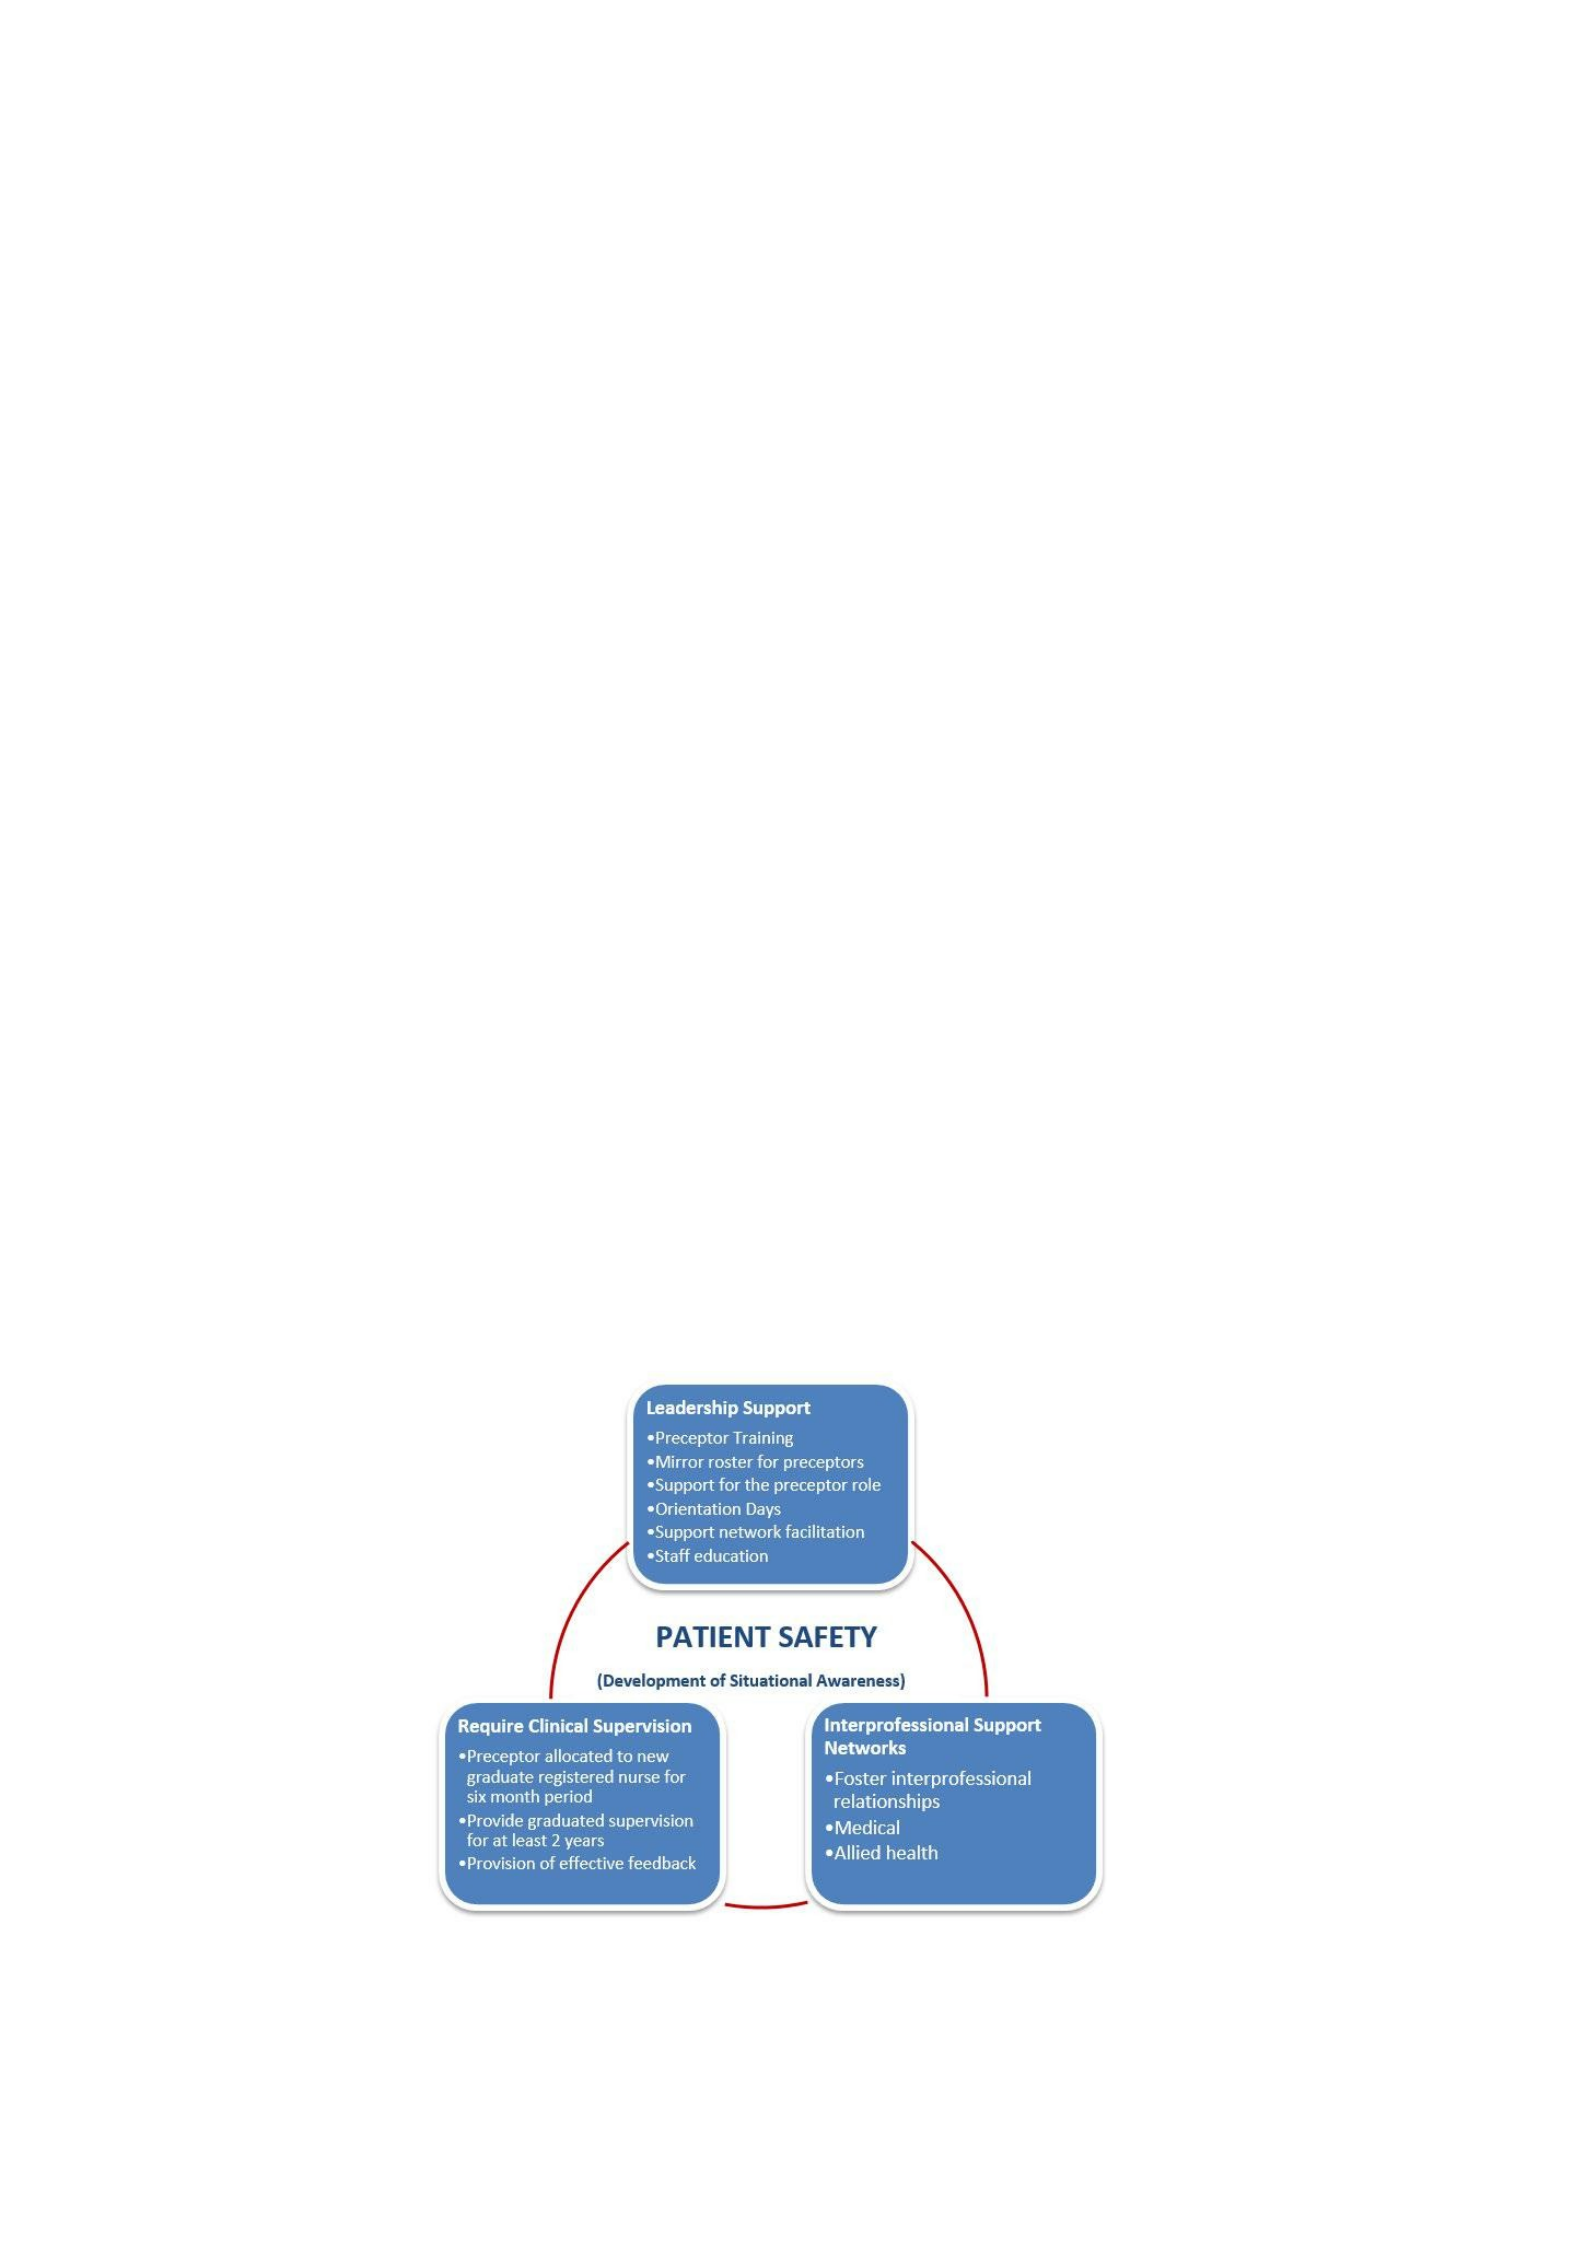
Three core elements for an effective transition to practice program
Three core elements of a transition to practice program that ensure patient safety and develop
situational awareness are 1) leadership support, 2) need for clinical supervision, and 3)
development of interprofessional relationships. These three core elements need to be
implemented for a transition program to be effective.
Figure. 3: Three core elements that ensure transition to practice for new graduates is focused on patient safety

Implementing the recommended three core elements of the transition to practice program will
assist novice registered nurses to work within their scope of practice. When NGRN’s report feeling
overwhelmed or feel an activity is beyond their capacity they should be able to voice these
concerns and also have them acted upon.
Nurses are accountable for making professional judgments about when an activity is beyond
their own capacity or scope of practice and for initiating consultation with, or referral to,
other members of the health care team. (NMBA, 2008a, p.6)
Issues of empowerment were evident as new graduates in this study did not appear to have a
voice with regard to their scope of practice concerns. These concerns have implications for
nurse registration authorities with regard to public safety and need to be addressed (El Haddad,
et al., 2013; Wu et al., 2012).
Limitations and recommendations for further study
This study was undertaken in South Australia and represents the transition experience of new
graduate registered nurses from three clusters of rural hospitals. Each of the rural hospitals
had unique characteristics that defined them and this may have implications with regard to
transferability of the findings. Other limitations include the lack of opportunity for focus group
participants to verify our interpretations and thematic analysis.
Two recommendations have been determined for further study. The first is to undertake further
study of new graduate transition and the implications for patient safety; the second is to
investigate the reasons why the three core elements, so essential to transition to practice
programs, are not routinely implemented.
Implications for nursing
In an international context there needs to be a major shift in policy when providing transition to
practice programs to NGRN’s in rural areas. It is imperative that rural health services that intend to
offer places to NGRN’s have the resources available to deliver the essential three core elements of
a transition to practice program - the need to mandate clinical supervision; the need for leadership
support and the need for development of interprofessional support. It is also recommended that
nurse registering authorities reflect on these three core elements and make a commitment to
public safety by mandating that NGRN’s have appropriate support and work within their scope of
practice. This will ensure patient safety and an effective, sustainable rural health workforce (El
Haddad et al., 2013).
Conclusion
The historical focus on graduate nurse transition as a “period of adjustment” understates the
implications for patient safety. This study ‘the nature of professional support given to new graduate
registered nurses’ emphasized the need for transition programs to have a focus on patient
safety.

Participants reported there was often a significant difference between the support promised in
formal transition to professional practice programs and that actually provided. Secondly, NGRN’s
found they were disempowered or did not have a voice to address their scope of practice
concerns. There were few places for them to turn to have these concerns addressed when they
felt out of their depth, contrary to the expectations of nurse registration authorities. An effective
transition to practice program is an attainable goal if the three core elements identified in this study
are implemented: leadership support, clinical supervision, and effective inter-professional
relationships. Further research by nurse registration authorities toward developing a regulatory
model for transition to practice within an international framework is recommended. Regulating the
three core elements of a registered nurse transition to practice program may be essential.
References
Ashcraft, A. S. (2004). Differentiating between pre-arrest and failure-to-rescue. Medsurg
Nursing, 13(4), 211-215.
Benner, P. (1984). From novice to expert, excellence and power in clinical nursing practice.
New Jersey USA: Prentice-Hall.
Benner, P., Tanner, C. A., & Chesla, C. A. (1996). Expertise in nursing practice: caring, clinical
judgment, and ethics. New York: Springer Publishing Company.
Bjørk, I. T. & Kirkevold, M. (1999). Issues in nurses’ practical skill development in the
clinical setting. Journal of Nursing Care Quality, 14(1), 72-84.
Boychuk Duchscher, J. E. (2009). Transition shock: the initial stage of role adaptation for
newly graduated registered nurses. Journal of advanced nursing, 65(5), 1103.
Clare, J., & Vanloon, A. (2003). Best practice principles for the transition from student to
registered nurse. Collegian, 10(4), 25-30.
Commonwealth Department of Education Science and Training. (2002). Rural nurses: Knowledge and
skills required by registered nurses to meet the meet the challenges of a changing work environment
in the 21st century: A review of the literature. Australian Government Publication.
Cubit, & Ryan, B. (2010). Tailoring a graduate nurse program to meet the needs of our
next generation of nurses. Nurse Education Today, 31, 65-71.
Department of Human Services - Nursing. (2004). Transition to professional practice
subcommittee report. South Australian Government Publication.
Dougherty, M., & Larson, E. (2005). A review of instruments measuring nurse-physician
66

collaboration. The Journal of Nursing Administration, 35(5), 244.
Dracup, K., & Bryan-Brown, C. W. (2004). From novice to expert to mentor: shaping the future.
American Journal of Critical Care, 13(6), 448-450.
Duchscher, J. B. (2008). A process of becoming: the stages of new nursing graduate
professional role transition. Journal of Continuing Education in Nursing, 39(10), 441-450.
El Haddad, M., Moxham, L., & Broadbent, M. (2013). Graduate registered nurse practice
readiness in the Australian context: an issue worthy of discussion. Collegian: Journal of the
Royal College of Nursing Australia(0). doi: http://dx.doi.org/10.1016/j.colegn.2012.09.003
Etheridge, S. A. (2007). Learning to think like a nurse: stories from new nurse graduates.
Journal of Continuing Education in Nursing, 38(1), 24-30.
Fern, E. F. (2001). Advanced focus group research. California USA: Sage Publications.
Francis, K. L., & Mills, J. E. (2011). Sustaining and growing the rural nursing and midwifery
workforce: understanding the issues and isolating directions for the future. Collegian: Journal of
the Royal College of Nursing Australia, 18(2), 55-60. doi: 10.1016/j.colegn.2010.08.003
Glaser, B. G. (1967). The discovery of grounded theory strategies for qualitative research.
New York USA: Aldine Publishing Company
Glaser, B. G. (1992). Basics of grounded theory analysis. California USA: Sociology Press.
Greenwood, J. (2000). Critique of the graduate nurse: an international perspective. Nurse
Education Today, 20(1), 17-23. doi: http://dx.doi.org/10.1054/nedt.2000.0424
Hoffart, N., Waddell, A., & Young, M. B. (2011). A model of new nurse transition.
Journal of Professional Nursing, 27(6), 334-343. doi: 10.1016/j.profnurs.2011.04.011

