



A CHILD IN DISTRESS 2
Theo – A Child in Distress
Client Concerns
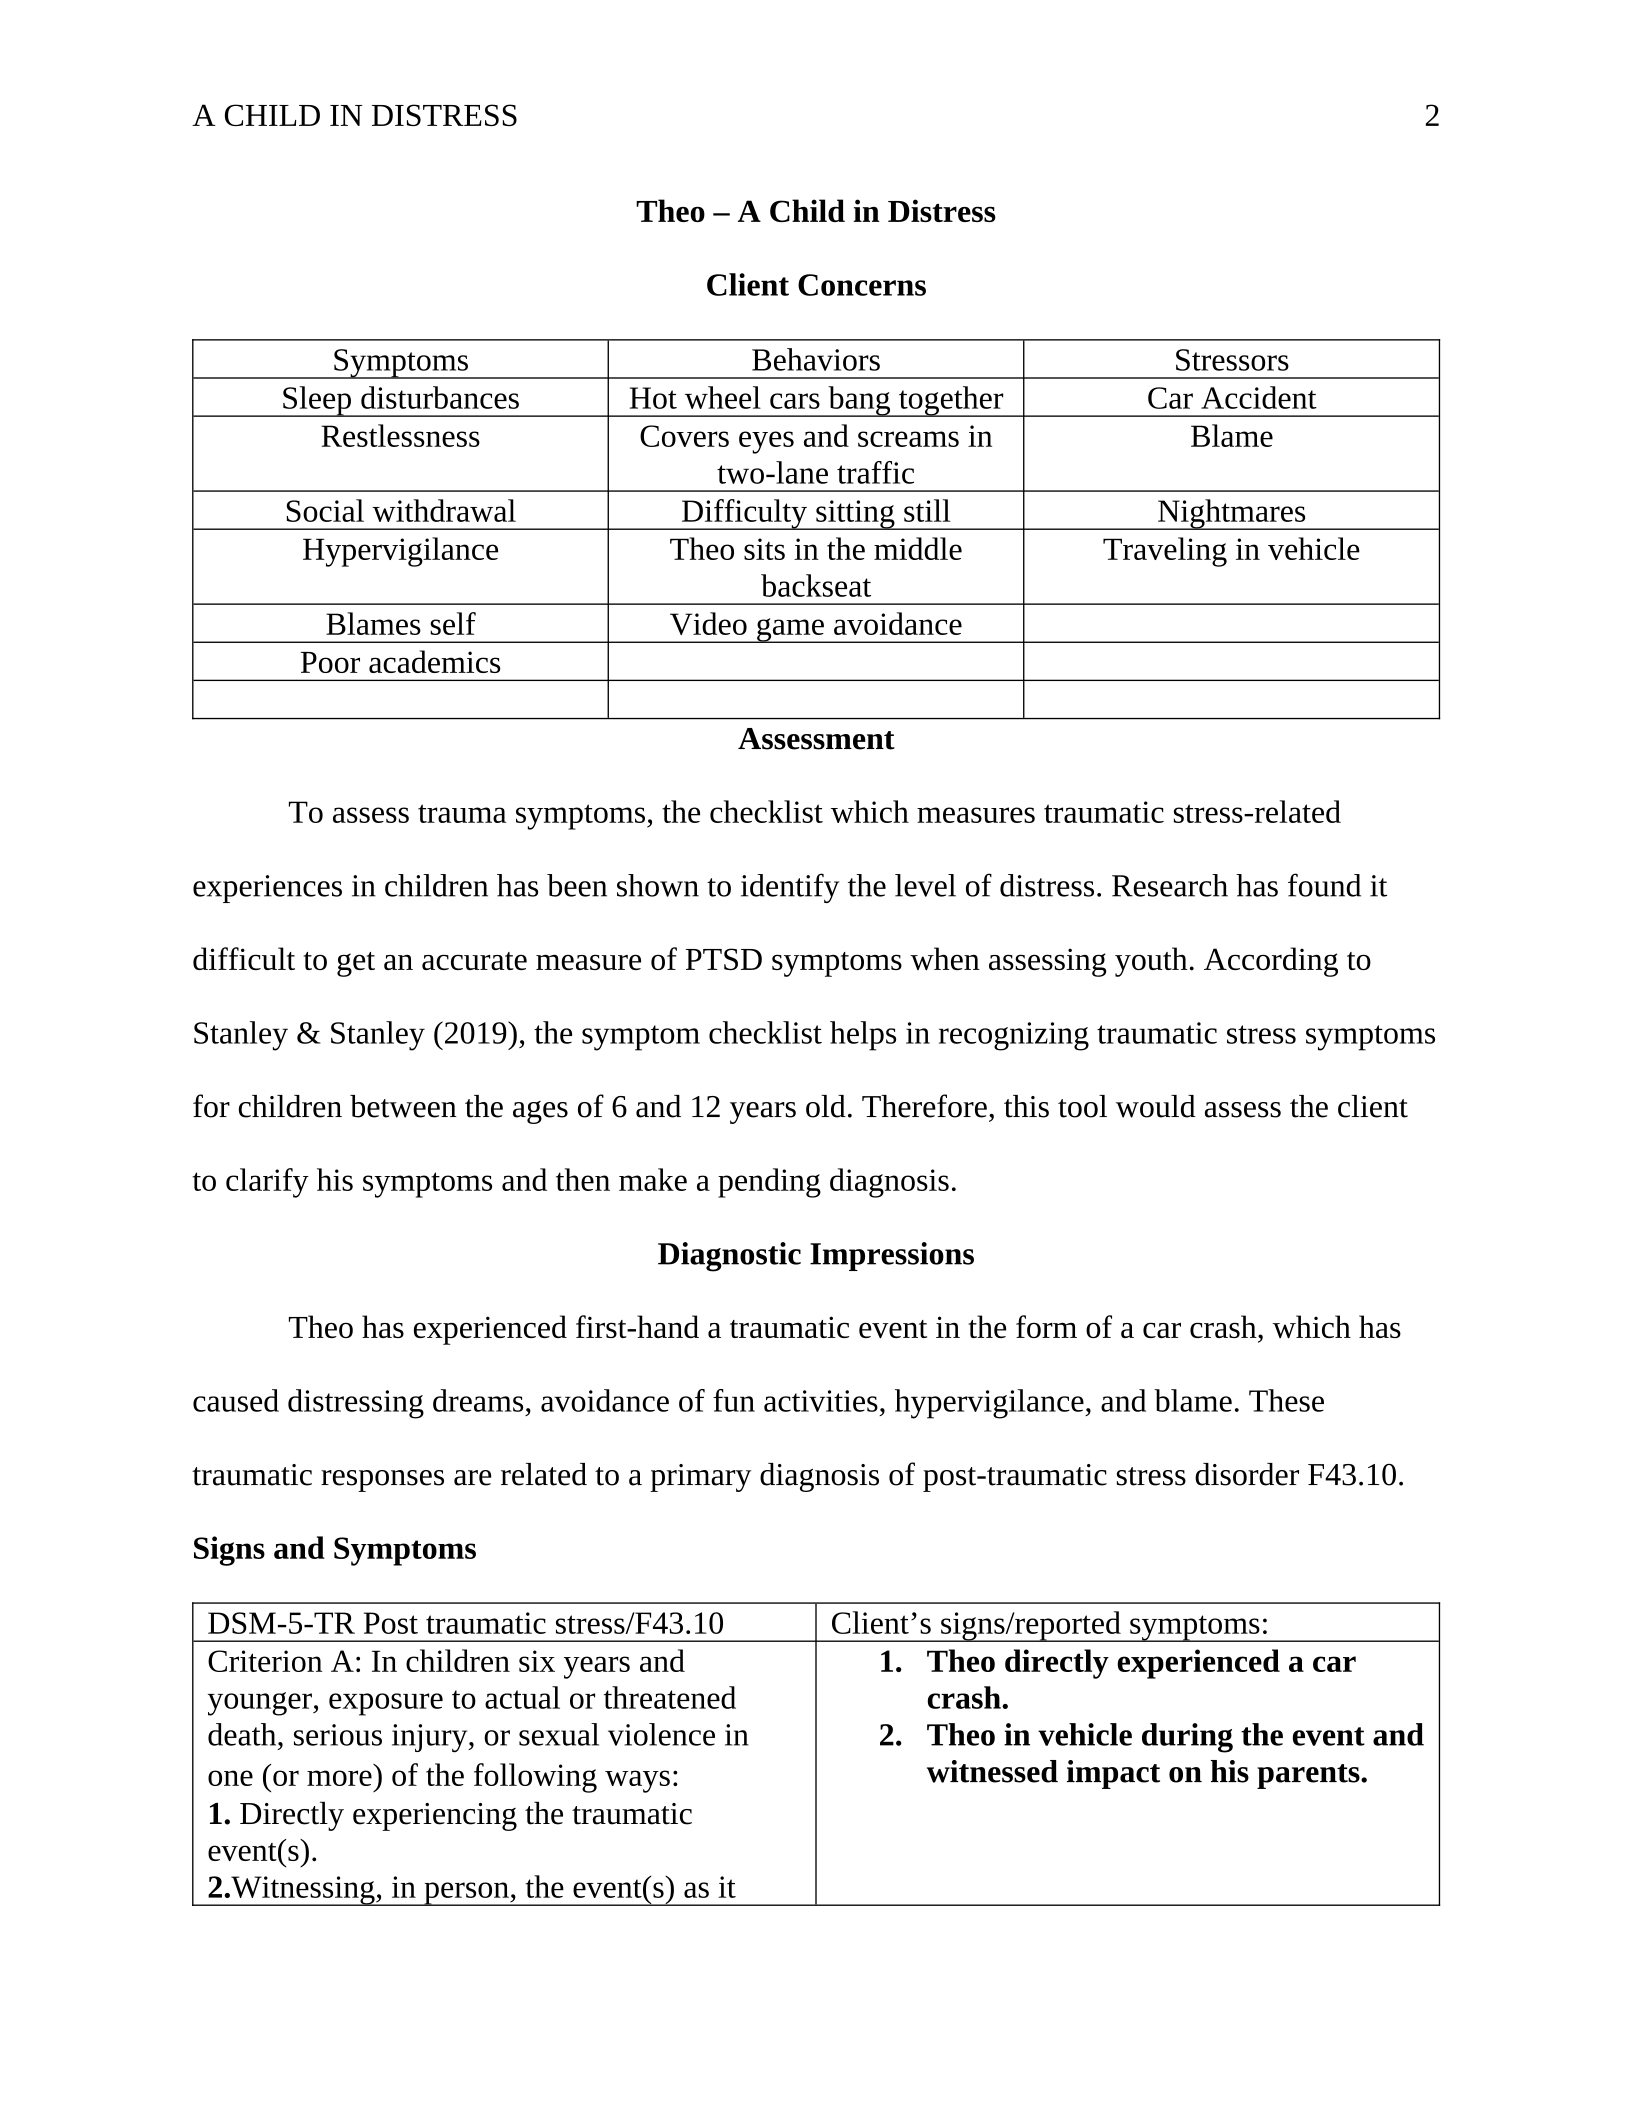
Symptoms Behaviors Stressors
Sleep disturbances Hot wheel cars bang together Car Accident
Restlessness Covers eyes and screams in
two-lane traffic
Blame
Social withdrawal Difficulty sitting still Nightmares
Hypervigilance Theo sits in the middle
backseat
Traveling in vehicle
Blames self Video game avoidance
Poor academics
Assessment
To assess trauma symptoms, the checklist which measures traumatic stress-related
experiences in children has been shown to identify the level of distress. Research has found it
difficult to get an accurate measure of PTSD symptoms when assessing youth. According to
Stanley & Stanley (2019), the symptom checklist helps in recognizing traumatic stress symptoms
for children between the ages of 6 and 12 years old. Therefore, this tool would assess the client
to clarify his symptoms and then make a pending diagnosis.
Diagnostic Impressions
Theo has experienced first-hand a traumatic event in the form of a car crash, which has
caused distressing dreams, avoidance of fun activities, hypervigilance, and blame. These
traumatic responses are related to a primary diagnosis of post-traumatic stress disorder F43.10.
Signs and Symptoms
DSM-5-TR Post traumatic stress/F43.10 Client’s signs/reported symptoms:
Criterion A: In children six years and
younger, exposure to actual or threatened
death, serious injury, or sexual violence in
one (or more) of the following ways:
1. Directly experiencing the traumatic
event(s).
2.Witnessing, in person, the event(s) as it
1. Theo directly experienced a car
crash.
2. Theo in vehicle during the event and
witnessed impact on his parents.
A CHILD IN DISTRESS 3
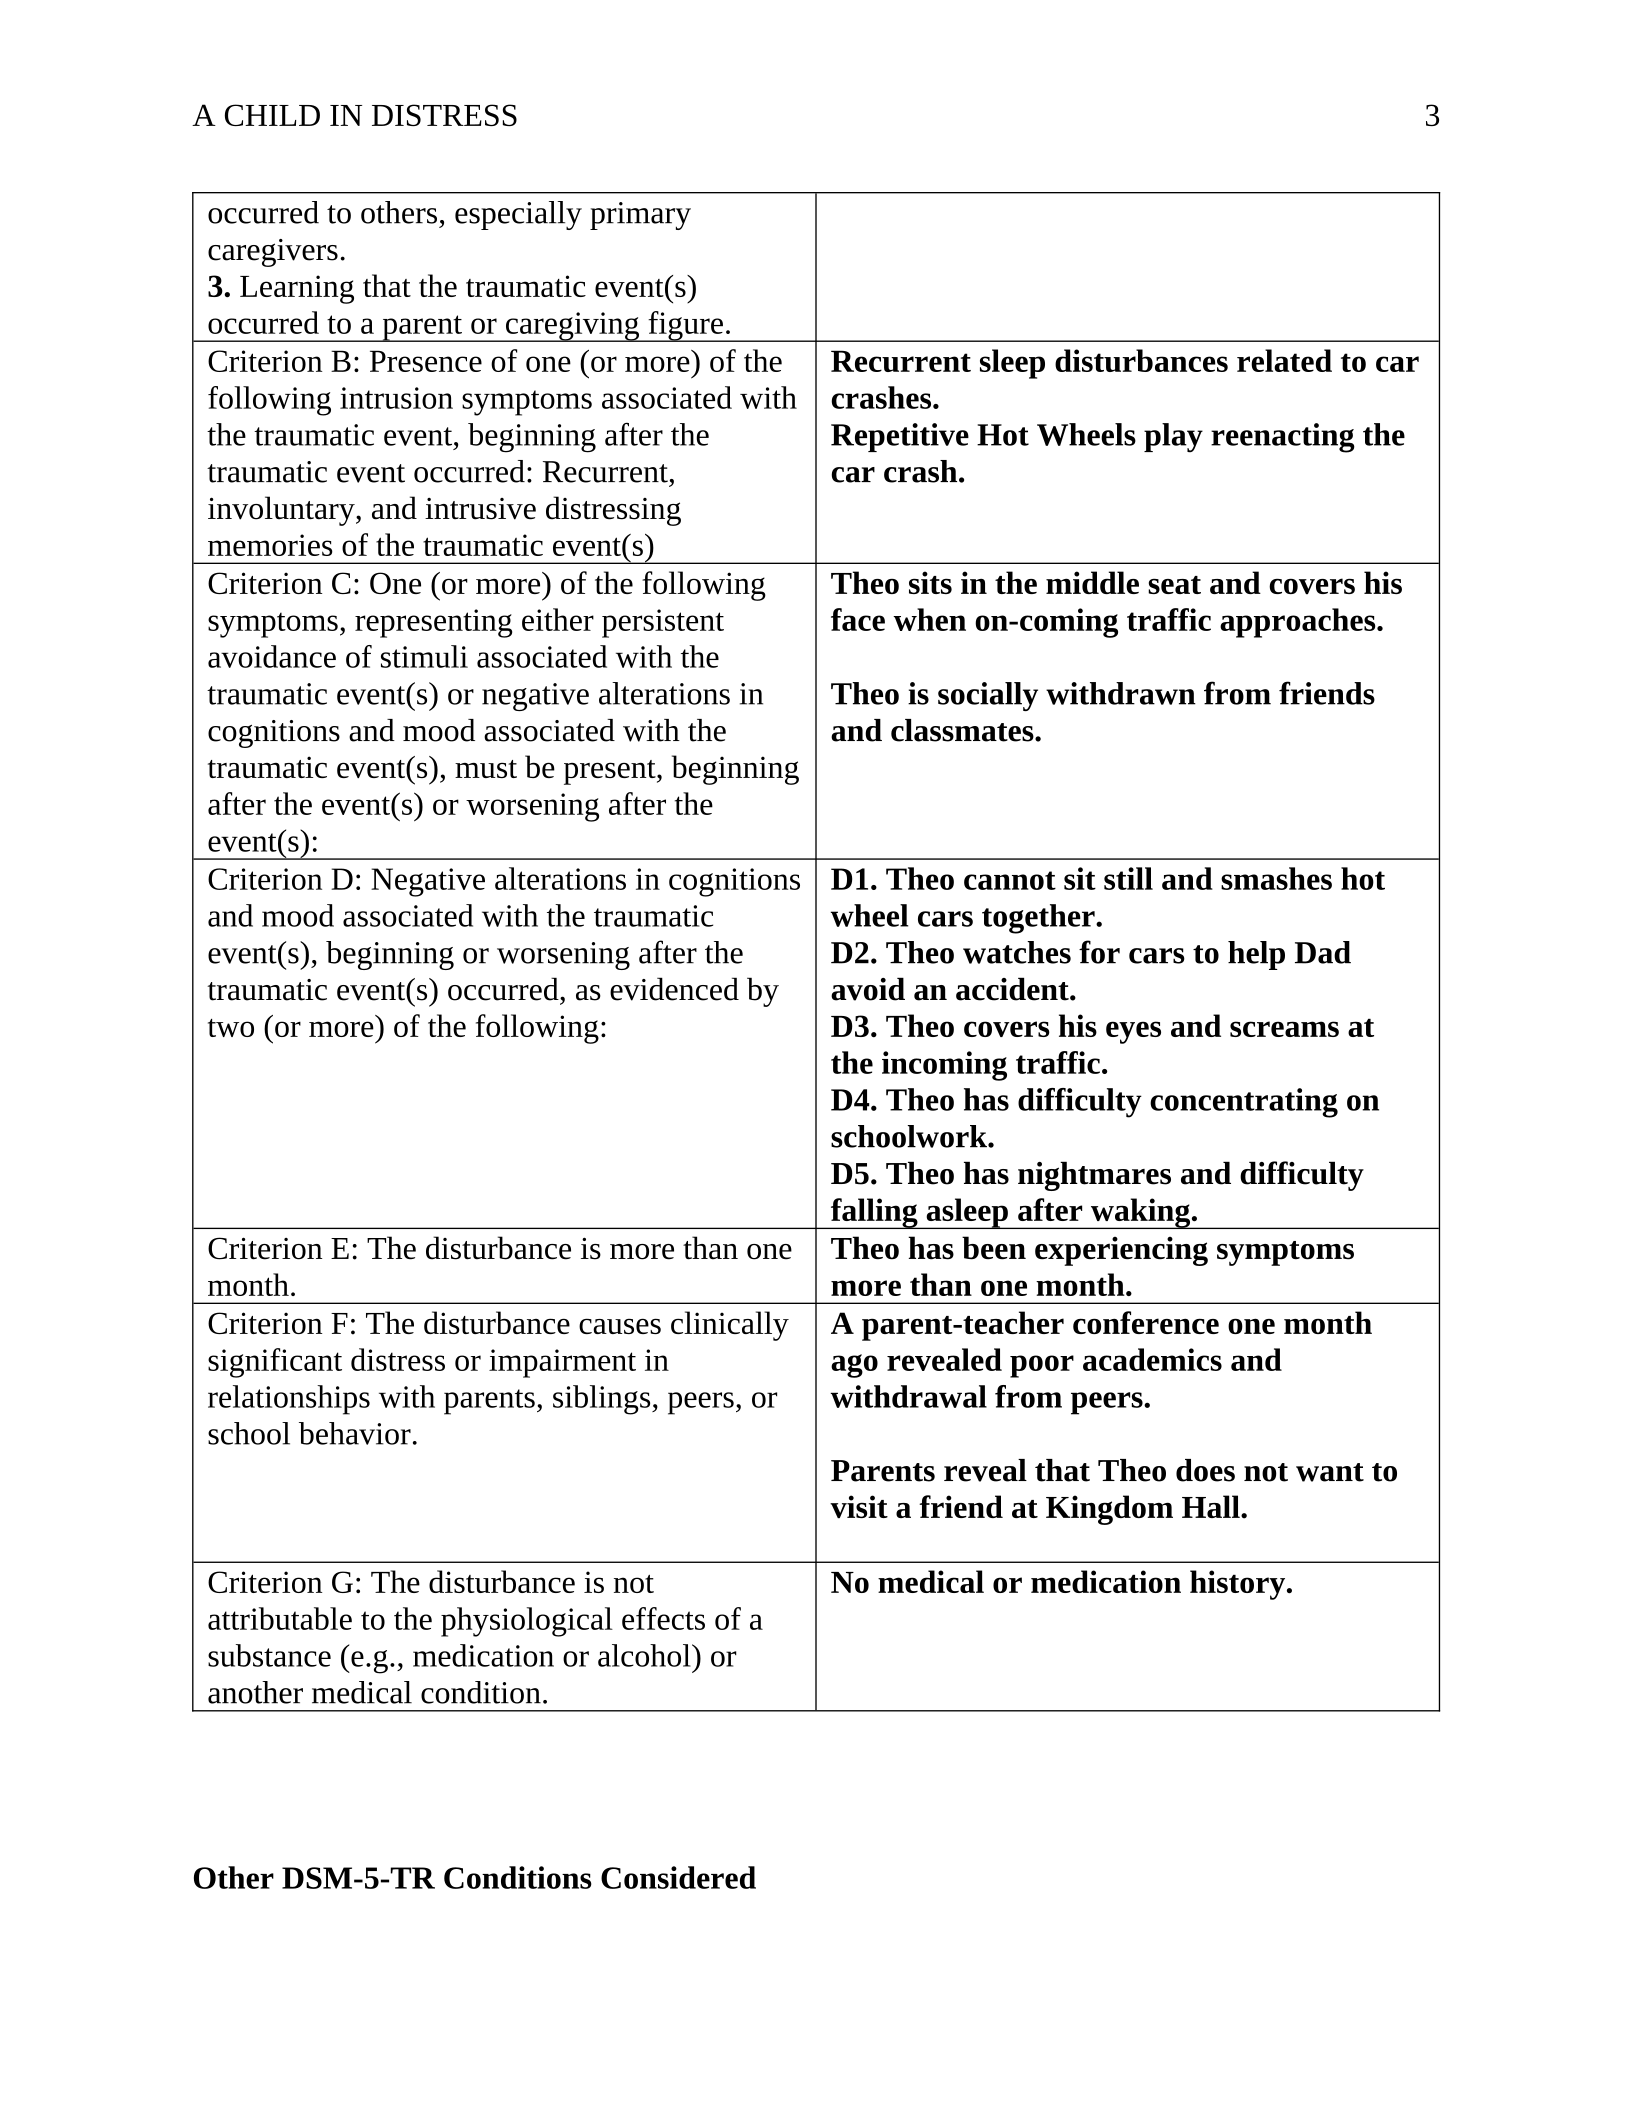
occurred to others, especially primary
caregivers.
3. Learning that the traumatic event(s)
occurred to a parent or caregiving figure.
Criterion B: Presence of one (or more) of the
following intrusion symptoms associated with
the traumatic event, beginning after the
traumatic event occurred: Recurrent,
involuntary, and intrusive distressing
memories of the traumatic event(s)
Recurrent sleep disturbances related to car
crashes.
Repetitive Hot Wheels play reenacting the
car crash.
Criterion C: One (or more) of the following
symptoms, representing either persistent
avoidance of stimuli associated with the
traumatic event(s) or negative alterations in
cognitions and mood associated with the
traumatic event(s), must be present, beginning
after the event(s) or worsening after the
event(s):
Theo sits in the middle seat and covers his
face when on-coming traffic approaches.
Theo is socially withdrawn from friends
and classmates.
Criterion D: Negative alterations in cognitions
and mood associated with the traumatic
event(s), beginning or worsening after the
traumatic event(s) occurred, as evidenced by
two (or more) of the following:
D1. Theo cannot sit still and smashes hot
wheel cars together.
D2. Theo watches for cars to help Dad
avoid an accident.
D3. Theo covers his eyes and screams at
the incoming traffic.
D4. Theo has difficulty concentrating on
schoolwork.
D5. Theo has nightmares and difficulty
falling asleep after waking.
Criterion E: The disturbance is more than one
month.
Theo has been experiencing symptoms
more than one month.
Criterion F: The disturbance causes clinically
significant distress or impairment in
relationships with parents, siblings, peers, or
school behavior.
A parent-teacher conference one month
ago revealed poor academics and
withdrawal from peers.
Parents reveal that Theo does not want to
visit a friend at Kingdom Hall.
Criterion G: The disturbance is not
attributable to the physiological effects of a
substance (e.g., medication or alcohol) or
another medical condition.
No medical or medication history.
Other DSM-5-TR Conditions Considered

A CHILD IN DISTRESS 4
Generalized anxiety disorder was considered due to restlessness, difficulties
concentrating, and excessive worry. Nevertheless, the worry was attributed to an actual event
that took place and was experienced. Therefore, generalized anxiety disorder would not apply.
Additionally, acute stress disorder was considered as the severity of the symptoms and the
timetable in which the event took place appeared to be correlated. Nevertheless, acute stress
disorder is restricted to a shorter duration following a traumatic event. The client's exposure took
place beyond the one-month threshold.
Developmental Theories and Systemic Factors
Constructivist theorists purport that children have specific knowledge about the world,
and through experiences, their knowledge develops (Saracho, 2023). This knowledge is reflected
in the client's experience using physical behaviors like smashing toy cars together after a traffic
crash. Jean Piaget would refer to this as physical knowledge, based on objects’ physical actions.
In this intellectual stage of development, Theo would be in the preoperational stage, which is
between the ages of 2 and 7 years, transitioning through his experience and social transmission
of his experience (Saracho, 2023).
Multicultural and Social Justice Considerations
Saleem et al. (2020) highlight how children aged six and under may have difficulty
processing traumatic events due to their lack of ability to reason and understand the experience.
This concept is especially true for children of color who have experienced a traumatic event. The
prevalence of traumatic exposure is higher among African American youth than their white
counterparts throughout their lifetime, so experiencing a profoundly stressful event at such a
young age impacts the overall well-being and traumatic response of the individual. Furthermore,
experiencing the actual event and witnessing a loved one's experience threatens the sense of

A CHILD IN DISTRESS 5
safety and security for oneself and that loved one, which impairs daily functioning and leads to
social avoidance (Saleem et al., 2020).
In addition to the ethnic and well-being considerations, Theo and his family are affiliated
with Jehovah's Witnesses. Within this faith tradition, death and the afterlife play a significant
role, which could be why he avoided Kingdom Hall. They did report that he was at the clinic
because he was scared he was going to die (Ringnes et al., 2019). This should be explored in
future sessions with Theo and the family as it could impact Theo's faith perspective later in life
and throughout adulthood.
Treatment Recommendations
Key Issues for Treatment
Sleep disturbances that cause difficulty staying and falling asleep.
Heightened sense of hypervigilance.
Social withdrawal from friends and classmates
Recommendations for Individual Counseling
The first treatment recommendation for Theo would be trauma-focused cognitive
behavioral therapy. Treatment has been shown to significantly improve children's mental health
and negative traumatic responses related to PTSD, depression, and anxiety (Palfrey et al., 2023).
This model is most effective when individual sessions with the child are combined and
conducted concurrently with family sessions with parents. According to Palfrey et al. (2023),
children displayed an increased desire for fun activities, peer relationships, and fewer sleep
disturbances. An item related to considerations is medication, which would be a "hard" no for
this client. At six years old, Theo can process information and impact his personal experience
through other interventions.

A CHILD IN DISTRESS 6
A second treatment recommendation is narrative therapy, which can help change the way
Theo views himself and help him re-author his story in a positive light. In a comparable case
study, an eight-year-old experiencing a similar car crash engaged in therapy that focused on
memories, meanings, and management using trauma memory narrative. This focus aids in
deconstructing the problem-saturated story to externalize and re-author it (Goodall et al., 2017).
The stories a youth tells themselves are often based on messages received from their families. By
opening a cognitive space, one can see the possibilities that can take place as they work through
a trauma narrative.
Specific Considerations
This case study presents the opportunity for a trauma-informed treatment approach
through various options. Regarding narrative therapy, as a clinician, story development can be
used in journaling and expanding on the story during each session as the narrative shifts. This
approach also puts the client in the driver's seat and offers a collaborative approach that would be
extremely helpful for a young child. The barriers that may be encountered are the age of the
client and his reluctance to engage in or understand the therapeutic process. To address these
barriers, creative methods can be used to provide a sense of comfort and security, such as
narrative play therapy, changing the environment to be more comfortable, and offering
expressive ways to communicate. Freeman et al. (1997) notes that letters, arts, sharing positive
news, and including the parents and siblings in the process can be playful ways to assist youth.

A CHILD IN DISTRESS 7
References
Freeman, J., Epston, D., Lobovits, D. (1997). Playful approaches to serious problems: Narrative
therapy with children and families. New York: W.W. Norton.
Goodall, B., Chadwick, I., McKinnon, A., Werner‐Seidler, A., Meiser‐Stedman, R., Smith, P., &
Dalgleish, T. (2017). Translating the cognitive model of PTSD to the treatment of very
young children: A single case study of an 8‐year‐old motor vehicle accident
survivor.Journal of Clinical Psychology,73(5), 511-
523. https://doi.org/10.1002/jclp.22449
Palfrey, N., Ryan, R., & Reay, R. E. (2023). Implementation of trauma-specific interventions in a
child and adolescent mental health service.Journal of Child and Family Studies,32(6),
1722-1735. https://doi.org/10.1007/s10826-022-02467-y
Ringnes, H. K., Demmrich, S., Hegstad, H., Stålsett, G., & Danbolt, L. J. (2019). End time and
emotions: Emotion regulation functions of eschatological expectations among Jehovah's
Witnesses in Norway.IJournal of Empirical Theology,I32(1), 105-
137. https://doi.org/10.1163/15709256-12341385
Saleem, F. T., Anderson, R. E., & Williams, M. (2020). Addressing the “Myth” of racial trauma:
Developmental and ecological considerations for youth of color.Clinical Child and
Family Psychology Review,23(1), 1–14. https://doi.org/10.1007/s10567-019-00304-1
Saracho, O.N. (2023). Theories of child development and their impact on early childhood
education and care. Early Childhood Education Journal 51(1), 15-30.
https://doi.org/10.1007/s10643-021-01271-5.


