


Pharm Test 2 Study Guide
Chapter 12
Informaion to pay atenion to in Neuropharmacology
•Study of drugs that alter processes controlled by the CNS
•Drugs can either excite or depress neuronal acivity
•A neuropharmacologic agent can alter one of two basic neuronal aciviies:
•Axonal conducion
•The process of conducing an acion potenial down the axon of the neuron
•Drugs that afect this process are not very selecive; alters conducion in all the
nerves it has access to; therefore, they have limited uses
1. Example: local anestheics non-selecively decrease axonal conducion
(look at diagram in book; lidocaine afects every single axon that it
comes in contact with; thus, when we give local anestheic, we inject it
to keep it localized to a speciic area
•Synapic transmission
•The process by which informaion is carried across the gap between the neuron
and the postsynapic cell
•Most neuropharmacologic agents act by altering synapic transmission;
therefore, they are more selecive b/c they alter speciic neurotransmiters or
receptors.
•Except for local anestheics all neuropharmacologic drugs act by altering the
synapic transmission
•Key point: the impact of a drug on a neuronally regulated process is dependent on the ability of
that drug to directly or indirectly inluence receptor acivity on target cells.
•In general drugs do 2 things: enhance receptor acivaion or reduce receptor acivaion
•Acivaion—an efect on receptor funcion equivalent to that produced by the natural
neurotransmiter at a paricular synapse
•Steps in synapic transmission

•Step 1-Transmiter synthesis; for synapic transmission to take place molecules need to
be present in the nerve terminal (igure 12-2)
•Step 2-Transmiter storage-stored in vesicles at nerve terminals unil ime of release
•Step 3-Release of the neurotransmiter into the synapic gap
•Amphetamines (CNS simulants) represent drug that promote transmiter
release, and botulinum toxin inhibits transmiter release
•Step 4-Binding of the neurotransmiter to the receptor, causes a physiological change in
the body
•Many drugs act directly at receptors by either:
1. Binding to receptors and causing acivaion, e.g. agonists (morphine,
epinephrine, and insulin)
2. Bind to receptors and, thereby, blocking acivaion by other agents, e.g.
antagonists (naloxone, anihistamines, and propranolol.
3. Binding to receptors components and, thereby, enhancing receptor
acivaion by the natural transmiter at the site, e.g. benzodiazepines:
diazepam (Valium),
•Step 5-Terminaion of transmiter acion, that is, the degradaion process.
•Transmiter can be removed from the synapic gap by 1. Reuptake, 2. Enzymaic
degradaion or 3. Difusion away from the synapic gap.
Chapter 13
Nervous system divided into central nervous system (CNS) and peripheral nervous system.
CNS=brain and spinal cord
Peripheral nervous system= somaic motor system and autonomic nervous system (sympatheic
and parasympatheic).
Major neurotransmiters of the peripheral nervous system are:
acetylcholine (secreted by cholinergic nerve ibers; employed at most juncions of PNS;
Acetylcholine is released by
1. Pre ganglionic neurons of PNS
2. All pre ganglionic neurons of the Sympatheic nervous system and
3. ALL POST GANGLIIONIC neurons of the Parasympatheic Nervous system
4. all motor neurons to skeletal muscles, and
5. most post ganglionic neurons of the sympatheic nervous system that go to sweat glands

norepinephrine (secreted by adrenergic nerve ibers; released by
1. Pracically all postganglionic neurons of Sympatheic nervous systems excepions – post
ganglionic sympatheic neurons that go to sweat gland which employ acetylcholine as
their transmiter
2. Also some is released by the adrenal medulla
epinephrine (secreted by the adrenal medulla)
dopamine ( acts as a catecholamine)
Receptor types
cholinergic receptor are deined as receptors that mediate responses to acetylcholine
othree subtypes: nicotinicN, nicotinic , and muscarinic
M
oa subtype responds to the same neurotransmitter but
nonetheless is diferent from other subtypes
adrenergic receptors are deined as receptors that mediate responses to epinephrine
(adrenaline) and norepinephrine (NE)
ofour adrenergic subtypes: alpha1, alpha2, beta1, and beta2
oanother adrenergic type: Dopamine receptors
do not respond to epinephrine or NE, only to dopamine, a neurotransmiter
found primarily in the CNS
Dopamine receptors are located in vasculature of the kidney; acivaion dilates
renal blood vessels increasing renal perfusion.
Can give these neurotransmiters exogenously to control the body pharmacologically
Autonomic nervous system
1. 3 primary funcions of the ANS: regulaion of the heart, secretory glands (salivary,
gastric, sweat, and bronchial glands), and smooth muscles (muscles of bronchi, blood
vessels, urogenital system, and GI tract).
2. A branch of the CNS
3. Regulated by the: hypothalamus, brain stem, and spinal cord
4. Requires no conscious or acion (just happens)
5. Maintains homeostasis by regulaing processes such as body temperature, responds to
stress and emergencies
6. Nerve impulses are transmited in the same way as the CNS
ANS is divided into Sympatheic Nervous System (SNS) and Parasympatheic Nervous system (PNS)
The two systems keep each other in balance. The SNS excites and the PNS inhibits.
1. The branch of the ANS that controls organ funcion most of the ime is said to provide
the predominant tone to that organ. In most organs, the PNS provide the predominant
tone. The vascular system, which is regulated almost exclusively by the SNS, is the
principle excepion.
2.

Parasympatheic funcions: slow heart rate, increase gastric secreion, empty
bladder, empty bowel, focus the eye for near vision, constrict the pupil, and
contract bronchial smooth muscle
Sympatheic funcions (3 main funcions): regulate cardiovascular system
(maintain blood low to the brain and other vital organs, redistribute blood low
during exercise, vasoconstricion to compensate for blood loss), regulate body
temp, and implement the ight or light reacion (increased HR/BP/CO, shuning
of blood away from the skin and viscera and into the skeletal muscles, dilaing
the bronchi to improve oxygenaion, dilaing pupils to enhance visual acuity,
mobilize store energy to provide glucose for the brain and faty acids for
muscles).
What you need to know about the ANS:
Drugs can act at 2 diferent sites in the PNS and SNS:
1. Synapses between preganglionic neurons and postganglionic neurons
Ganglion-neurons synapse in the ganglion; ganglion is a lump of nerve cell
bodies
One excepion is in the SNS where the adrenal medulla is looked on as the
equivalent of a postganglionic neuron b/c it inluences the body by releasing
epinephrine
2. The juncions between postganglionic neurons and their efector organs.
Drugs that afect the somaic motor system have one site of acion: the neuromuscular juncion
Fig 13-4: In order to understand PNS pharmacology, you must be able to idenify the
transmiters employed at each of the juncions of the peripheral nervous system
1. All preganglionic neurons of the PNS and SNS release acetylcholine as their transmiter
2. All postganglionic neurons of the PNS release acetylcholine as their transmiter
3. Most postganglionic neurons of the release SNS norepinephrine (NE) as their
transmiter
4. Postganglionic neurons of the SNS that innervate sweat glands release acetylcholine as
their transmiter
5. Epinephrine is the principle transmiter released by the adrenal medulla
6. All motor neurons to skeletal muscles release acetylcholine as their transmiter
The process of feedback regulaion is called a relex (arc); main elements of feedback regulaion:
1. Sensor-neuron picks up informaion, which is sent to the brain via the spinal cord
2. CNS: in the brain the informaion is integrated with other relevant info
3. Neurons- signals (instrucions for change) are sent from the CNS along the nerves of the
ANS to the efector
4. Efector—the muscle, organ; in response to these instrucions, the efector makes
appropriate adjustments in the process.

Adrenergic Agonists-Chapter 17
Produce efect by acivaing adrenergic receptors- similar to sympatheic nervous system
Adrenergic oten referred as sympathomimeics – used for heart failure, asthma, preterm labor.
Drugs that mimic the efects of adrenergic nerve simulaion (i.e. Mimic norepinephrine or mimic
the efects of the adrenal medulla releasing epinephrine)
Adrenergic Agonist Mechanism of Acion:
1. Direct receptor binding: the direct-acing receptor simulants produce their efect by binding to
adrenergic receptors and mimicking the acions of natural transmiters (NE, Epinephrine,
dopamine); this is the only mechanism that is direct; the next three are indirect
2. Promoion of NE release-act on terminals of sympatheic nerves to cause NE release. Examples:
Amphetamines and ephedrine; however, ephedrine can also acivate adrenergic receptors
directly
3. Inhibiion of NE reuptake-block causes NE to accumulate within the synapic gap increase
receptor acivaion. Examples: cocaine, tricyclic anidepressant (e.g. imipramine); these work to
raise NE.
4. Inhibiion of NE inacivaion-increases the amount of NE available for release by inhibits its
inacivaion by monoamine oxidase (MAO)- this can enhance receptor acivaion
Catecholamines
CANNOT BE USED ORALLY; can only be given IV
oAcion of MONAMINE oxidase MOA and catechol O methyltransferase and COMT
located in liver enzymes destroy catecholamines; therefore, they cannot be given orally
b/c of short half life
oTherefore, if we want to turn the infusion of because of HTN, they will be out of the
body quickly
BRIEF DURATION OF ACTION
CANNOT CROSS BLOOD BRAIN BARRIER because they are polar molecules; posiive charge
prevents them from crossing BBB
Oxidaion cause catecholamines to turn pink or brown over ime; catecholamine soluions
should be discarded as soon as discoloraion develops
Structurally the same ethylamine; contain catechol group and an amine group. Simply a benzene
ring that has hydroxyl groups or two adjacent carbons

oEpinephrine, norepinephrine, Isoproterenol, Dopamine and dobutamine have three
common properies
Chemically have a catechol and an amine group- DINE
oDopamine
oDobutamine
oIsoproterenol
oNorepinephrine (NE)
oEpinephrine
oImportant in criical care!!!
Noncatecholamines
Have ethylamine do not contain the catechol moiety (a part or funcional group of a molecule)
that characterized the catecholamines
oEphedrine, Phenylephrine, terbutaline
Because they lack a catechol group, they are not substrates for catechol-O-methyltransferase
(COMT) and are metabolized slowly by MAO much longer half-lives and can be given PO
Structurally do not have the catechol porion of the molecule- PET
oPhenylephrine
oEphedrine
oTerbutaline
As compared to catecholamines:
oHave longer half-lives (not as metabolized in the liver)
oTherefore, they can be given orally
oLess polar thus cross the B-B barrier (more efects on the CNS)
RECAP: Important Diferences between Noncatecholamines and Catecholamines
Catecholamines: Not given orally; Brief duraion of acion; cannot cross blood brain barrier; DINE
(Dopamine, Dobutamine, Isoproterenol, Norepinephrine, Epinephrine)
Noncatecholamines: Lack catechol group- not substrates for COMT and MAO; Half-lives much longer;
Can be given orally; Less polar more able to cross blood brain barrier; PET (Phenylephrine, Ephedrine,
Terbutaline).
SNS—Fight or Flight response—Running from the BEAR
To either with stress or from itdeal run
Increased BP (increased CO and HR)
Increased cardiac output (CO)

Blood is shunted to the brain, heart, and skeletal muscle
Decreased blood low to the visceral organs (skin, kidneys)
Increased rate of cellular metabolism
Increased blood sugar; increased breakdown of muscle glycogen (to have energy to get away)
Increased mental acivity (think beter)
Increased coagulaion (don’t want to bleed to death if you fall down)
Increased respiratory rate and depth (b/c you’re running as fast as you can)
Pupil (to aid in vision) dilaion
The SNS receptors (adrenergic receptors)
Alpha 1:
Located in eyes, blood vessels, male sex organs, prostaic capsule, and bladder (trigone and
sphincter)
contract muscles; vasoconstricion; rise in BP; GI & bladder sphincter contracion; pupillary dilaion
(mydriasis)
Alpha 2:
Receptors of the peripheral nervous system are located on nerve terminals and not on the organs
innervated by the ANS.
Referred to as presynapic or prejuncional b/c they’re located on nerve terminals
Regulate neurotransmiter releases
negaive feedback, if you simulate alpha 2, you inhibit NE; inhibiing NT release, less norepinephrine
is released; thus, an aniadrenergic efect:
1) Reducion of sympatheic ouflow to the heart and blood vessels
2) Relief of severe pain
Beta 1:
receptors located in the heart and kidney
acivaion of cardiac receptors increases the rate and force of contracion, and velocity of impulse
conducion through the AV node
acivaion of the receptors in the kidney causes the release of Renin (precursor in RAS system) into
the blood; renin promotes synthesis of angiotensin, a powerful vasoconstrictor that raises BP
acivaion- heart failure
Shock
Atrioventricular heart block-drug used for cardiac arrest-epinephrine
Adverse efect of BETA ONE= Altered heart rate or rhythm, angina pectoris (b/c of
vasoconstricion)
Beta 2:

receptors located in the smooth muscles of the uterus, lungs, arterioles of the heart, lungs, and
skeletal muscle; also located in the liver
Inhibits smooth muscle; causes relaxaion of uterine and bronchial smooth muscle
(bronchodilaion); arterioles vasodilate
Acivaion in the skeletal muscles and liver promotes glycogenolysis(the breakdown of glycogen
into glucose) and ; it also enhances skeletal muscle contraciongluconeogenesis
Used for asthma, delay of preterm labor
Bronchodilaion in asthma (albuterol is a beta 2 agonist)
Beta Two adverse efect hyperglycemia and tremor
Dopamine:
Have receptors located in the peripheral and central nervous system
The only peripheral receptors are located in the renal vasculature
Acivaion of the receptors in the renal vasculature cause dilaion of blood vessels surrounding the
kidney; enhances renal perfusion
Parasympathetic nervous system
Rest, reparaive, vegetaive state
Aids in digesion, excreion, cardiac deceleraion, anabolism and near vision, balances out SNS
75% of all PNS ibers are in the vagus nerves
Body responses of the parasympatheic are basically the opposite of the SNS, not 100% opposite
Dilaion of blood vessels, decreased heart rate, increased secreion of digesive enzymes and moility
of the GI tract, bronchoconstricion, increased secreions from glands in lung, stomach, intesines
and skin, constricted pupils and accommodaion to near vision, contracion of smooth muscle of the
bladder
No noted efects on blood coagulaion, blood sugar, mental acivity or muscle strength
Regulaion of the PNS:
Acetylcholine regulates the PNS; regulaion PNS results in:
oPupil constricion
oBradycardia
oBronchoconstricion
oVasodilaion
oGI acivity
oVoiding
oErecion
oGeneralized sweaing
General informaion:
Most drugs simulate receptors but research is on-going to develop those that will work muliple
only on speciic receptors thus limiing efects
Terms which refer to substances that the SNS: simulate
Sympathomimeic-to simulate the SNS
Alpha and beta adrenergic agonists-simulate the body as the natural body chemicals would

Adrenergics, adrenomimeics, adrenergic agonists
Substances that simulate the PNS:
Direct-acing
Parasympathomimeic, cholinomimeic, cholinergics, cholinergic agonists
Indirect acing
Cholinesterase inhibitors (anicholinesterase)-increase muscle tone
Substances that the SNS:inhibit
Sympatholyic, aniadrenergic, alpha and beta blocking drugs, adrenergic blockers,
adrenolyics, adrenergic antagonists
Substances that inhibit PNS:
Parasympatholyic, anicholinergic, cholinergic blockers, cholinergic antagonists, or
anispasmodics
Key points:
Opposite responses on organ issue are caused by sympathomimeics and
parasympatheomimeics sympathlyics parasympatholyics, and by and .
Sympathomimeics parasympatholyics and cause similar organ response as do sympatholyics
and parasympathomimeics.
Applicaion to pracice: because sympathomimeics and parasympatholyics have similar
efects, when a pt. has asystole, alternate between epinephrine and atropine (a parasympatheic
depressant)
Adrenergic drugs
Produce efects similar to those when the SNS is simulated
Therapeuic efects and adverse efects are due to the inluence on blood vessels, lungs and
heart
Most body issues have both alpha and beta receptors
Thus efects depend mostly on each drug’s acivaion of paricular receptors and the number of
afected receptors in a paricular body issue
a. Alpha 1: vasoconstrict, elevate BP and decreases nasal congesion
b. Beta 1: cardiac simulaion (rate and force of contracion)
c. Beta 2: bronchodilaion, vasodilaion, contracion of urinary and GI sphincters, changes
in renin secreion (afects kidneys and luid balance), decreased secreion of insulin (thus
higher blood glucose)
Some Indicaions for Adrenergic Drugs
Treatment of respiratory, cardiac and allergic emergencies (epinephrine is one of the main drugs
we use from this category; allergic rxns)
Decongestants (colds, sinusiis); vasoconstricion of vessels in nose decreases congesion
Pre-term labor (decrease contracions)
Used a lot in crit care seing; when pts get sepic, they become very hypotensive; have to
maintain BP, so we use these drugs
Adrenergic Contraindicaions
Cardiac arrhythmias (simulaing the rate and force of the heart is not something we want to
do).
Angina
HTN
Hyperthyroidism (those pt. are oten tachycardia)
Severe anxiety states
Psychiatric disorders (due to CNS simulaion)-use caion
Elderly (use cauion)
Adrenergics Adrenalin (Epinephrine)
Simulates both alpha (1 and 2) and beta (1 and 2) receptors (all 4)
Mimics endogenous epinephrine
At usual doses: beta efects prevail; when we give a dose of epinephrine we usually see more
cardiac efects to try to force the heart to respond
At higher doses: alpha efects prevail (vasoconstricion); see more vasoconstricion
Uses:
a. Drug of choice for anaphylacic shock (to relieve bronchospasm and laryngeal edema)-
high dose
b. Used in cardiac arrest as a cardiac simulant and vasoconstrictor
c. Acive ingredient in OTC inhalaion asthma products (Primatene Mist, Bronkaid Mist);
recommend pt. experiencing anaphylacic atack not use these drugs b/c they will not
respond b/c receptors are already occupied; should use albuterol instead
Table 17-2, p. 155 KNOW THIS TABLE
Catecholamines Noncatecholamines
Drug Receptors acivated Drug Receptors acivated
Epinephrine α1, α 2, β1, β2 Ephedrine* α1, α 2, β1, β2
Norepinephrine α1, α 2, β1 Phenylephrine α1
Isoproterenol β1, β2 Albuterol β2
Dobutamine β1
Dopamine** α1, β1, dopamine
*Ephedrine is a mixed-acing agent that causes NE release and also acivates alpha and beta receptors
directly.
**receptor acivaion by dopamine is dose dependent.
Epi-Pen: DON’T LEAVE HOME WITHOUT IT
Mrs. O. says there will be a test quesion of the administraion of the Epi-pen.
EpiPen Descripion and dosage
Single-use, epinephrine auto-injector; used in anaphylacic emergency
Spring-acivated needle, designed for IM injecion
Two strengths: EpiPen (0.3 mg dose 66 lb or more); EpiPen Jr. (0.15mg between 33 and 66 lb)
Rx only, can give up to two injecions
EpiPen Storage and replacement
Epinephrine is sensiive to heat and light; store at room temperature in a dark place; don’t
refrigerate
If the epinephrine soluion turns brown, if a precipitate forms, or if the expiraion date has
passed, the unit should be replaced.
Who, When, and How?
Anyone who’s experienced a severe allergic rxn should carry an EpiPen
Administer as soon as early symptoms of anaphylaxis appear (swelling, SOB)

INJECTIONS MADE INTO OUTER THIGH:
1. Form a ist around the unit with the black ip poining down
2. With the free hand, pull of the gray acivaion cap
3. Jab the device irmly into the outer thigh, at an angle perpendicular to the thigh, and hold it
there for 10 sec (the injecion can be made directly through clothing)
4. Remove the unit and massage the area for 10 sec to facilitate absorpion
The EpiPen contains of epinephrine soluion, but only 0.3 ml is actually injected; there should 2 ml
sill be some soluion let in the device ater injecion
The device should be inspected for a protruding needle to ensure successful injecion
What should be done ater the injecion?
Get immediate medical atenion b/c
1. The efect of the epinephrine face in 10-20 min
2. Anaphylacic rxn can be biphasic and prolonged; hospitalizaion (up to 6 hrs) is
recommended
3. Hospital staf should be shown EpiPen to conirm dosage
4. Can have adverse efects: sweaing, dizziness, HA, N/V
Actions of Epinephrine
Increased BP: vasoconstricion to periphery and kidneys
Vasodilaion and increased blood low to vital organs
Increased HR , possibly arrhythmias as the conducion issue of the heart is simulated
Relaxaion of GI smooth muscle
Relaxaion/dilaion of bronchial smooth muscle
Increase glucose and faty acid in the blood, inhibiion of insulin producion
Increased rate of blood coagulaion
Decreased intraocular pressure in wide angle glaucoma
Epinephrine Routes-KNOW THE ROUTES
Not given PO: due to irst pass efect
IV, IM, inhalaion(down the ET tube; in emergency situaions when you don’t already have IV
access), topically, SC
Diluions difer in IV versus IM/SC: IV: 1:10,000; IM/SC: 1:1,000
When given by IV, it works quickly but has a short duraion; typically will repeat dose if person
does not respond.
Epinephrine Adverse effects
Increases in BP leading to hypertensive crisis (esp. with repeated doses)
Dysrhythmias (sinus tach); Any drug that treats arrhythmias can also cause another arrhythmia
Increases heart’s workload and oxygen demands (may cause angina); good thing that
epinephrine is short in duraion
Hyperglycemia- One should be aware that hyperglycemia can occur post Epi dosing in code
situaions!!!!
Ephedrine
Simulates both alpha and beta receptors
Simulates the release of norepinephrine
Less potent, but longer acing as compared to epinephrine
FDA recommended withdrawal from products due to risk of cardiac arrest; used to be available
in diet pills and sleep depressant drugs (keep you up at night)
Pseudoephedrine (Sudafed)
Related to ephedrine with similar acions
Bronchodilaion
Nasal congesion-by vasoconstricing vessels in nasal passages
Usually given PO
Allergy, cold remedies
Phenylephrine (neo-synephrine)
A syntheic that works on alpha receptors resuling in vasoconstricion
Does not simulate beta receptors
Given to increase BP in shock states and hypotension
Lasts longer than epi (20-50 minutes) but a relex bradycardia may result
Long duraion is one of the beneits over epinephrine (this is why it’s given as an infusion and
epinephrine isn’t)
Used to treat paroxysmal atrial tachycardia (PAT)
A nasal decongestant (topical) in cold and allergy remedies
Dopamine (Inotropin)
A catecholamine that acts by releasing endogenous norepinephrine
Given coninuous IV only
Short half-life (5-10 minutes); (2-5 minutes)Rapid onset
Indicaions:
oShock, Heart failure, Acute renal failure: acivaing Beta1 receptors in the heart increases
contracility/CO (improved issue perfusion) and acivaing Beta1 receptors in the
kidneys causes renal blood vessels dilaion (improved renal perfusion)
oAcute renal failure—new evidence pg 160: drug is not efecive; in pts with early ARF,
dopamine failed to protect renal funcion, shorten hospital stays, or reduce the number
of pts needing a kidney transplant. Time to abandon low-dose TX with dopamine for
ARF.
oUsed in intensive care unit seing; not used as much as previously: increase
CO/contracility
Diferent receptors afected at diferent doses:
oLow doses:(up to 2-3 mcg/kg/min) simulates dopaminergic receptors to cause
vasodilaion of the renal and mesenteric arteries (new evidence does not support this-
pg 160); don’t use it at this dose very much any more
oModerate doses: (2-10 mcg/kg/min) dopamine works on Beta 1 receptors on the
myocardium; increases cardiac output by increasing myocardial contracility and stroke
volume);
oHigher doses: (10-20 mcg/kg/min) alpha receptors are simulated; BP increases and CO
increases; renal blood low may decrease resuling in decreased urinary output due to
vasoconstricion
oAdverse efects are dose dependent: tachycardia, dysrhythmias, angina, headaches,
Nausea/Vomiing, hypertension

NE-norepinephrine (Levophed)
Used a lot in ICU
P 155, simulated alpha 1 and 2 and beta 1
The diference btw epinephrine and NE is that epinephrine simulates beta 2 receptors and NE
does not; for this reason, hyperglycemia is not an adverse efect (an adverse rxn mediated by
beta2 receptors)
Can cause such profound vasoconstricion that it can cause poor blood low in extremiies
Indicaions: hypotensive states and cardiac arrest; example: in pts with sepsis, controlling the
blood pressure is important b/c of difuse vasodilaion
Adrenergics: general points
Epinephrine (EPI) is the drug of choice in anaphylaxis, as an antagonist of histamine and other
bronchoconstricing and vasodilaing substances released in an anaphylacic reacion)
People who are taking beta blockers (lol drugs-beta antagonists) do respond as readily to EPI not
(beta agonist) as those who are not taking them. Thus, of EPI may be required in larger doses
order to overcome efect of beta antagonist acion.
In a resuscitaion situaion, EPI is the drug of choice for its vasoconstricion and cardiac simulant
efects
Overuse of nasal decongestant topical nasal sprays leads to a rebound congesion, decreases
efeciveness, and causes irritaion of the nasal mucosa. Thus, nasal decongestants shouldn’t be
used for more than 3-5 days. Eventually blood vessels are not able to maintain vasoconstricion
ater a while. Oral decongestants are alright, but overuse of topical decongestants can lead to
resistance.
Ephedrine and other adrenergic decongestants can cause in normotensive hypertension
paients; teach pts with HTN not to use sympathomimeics to TX colds b/c it can exacerbate their
HTN and throw them into a hypertensive crisis. Phenylephrine is beter tolerated than Sudafed,
so it is more likely to be used in hypertensive pts.
Antiadrenergics (block adrenergics)
Decrease or block efects of sympatheic nerve simulaion, endogenous catecholamines, and
adrenergic drugs
Goal of these drugs:
oSuppress the pathologic simulaion of the SNS, not the normal funcion of the SNS
oNormal basal acivity of the SNS is needed to regulate BP, blood sugar and the stress
response
oNormal response to acivity and stress should not be inhibited
Adrenergic Blockers=sympathetic depressants (Alpha 1)
Act on the skin, smooth muscle, mucosa, intesines, and kidneys to prevent alpha mediated
vasoconstricion
Speciic efects: dilaion of arterioles and veins, increased local blood low, decreased blood
pressure, pupil constricion, increased GI moility, decrease urinary retenion in BPH
Indicaions for use:

oUsed to be used for hypertension, but study found increased mortality with long-term
use; they did not do as well as diureics and beta blockers in decreasing mortality. EBP
(evidence based pracice)
oOnly use now for Benign Prostaic Hypertrophy (BPH)
Example:
oDoxazosin: (Cardura® used for hypertension and Benign Prostaic Hyperplasia (BPH)
oNot used much anymore for HTN- study showed trend for increased mortality
oOnly used in BPH currently
oOthers:
oTamsulosin -lomax used for BHP
oPrazosin-minipress –hypertension
Major side efect of Alpha1 blockage orthostaic hypotension high risk for falls, fracture,
complicaions such as pneumonia and mortality
Alpha 2 adrenergic agonists
Clonidine (Catapres): used for hypertension and hypertensive emergencies; one of the most
commonly anihypertensives used in hypertensive crisis
Methyldopa (Aldomet): an older drug used for hypertension
SE: hemolyic anemia, hepatotoxicity
Non-selecive Alpha Blockers
Used for pheochromocytoma- a rare tumor of the adrenal medulla that causes secreion of epi
and norepi (vasoconstricing substances) which results in:
oTachycardia
ohypertension (HTN)
ocardiac arrhythmias
Used for vascular diseases characterized by vasoconstricion (Raynaud’s and frostbite) to
increase blood low
Non-selective Adrenergic antagonists/blockers
Phentolamine (Regiine):
oused in pheochromocytoma
oused locally for issue necrosis from extravasaion of vasoconstrictors (such as dopamine
and norepinephrine)
oBlocks alpha 1 and alpha 2
oSE Orthostaic hypotension , relex tachycardia
Beta Blockers- lol
Occupy beta adrenergic receptor sites and prevent the receptors from responding to
sympatheic simulaion
Beta blockers prevent epi and norepinephrine from occupying sites
Examples of Beta blockers: Metoprolol, Carvedilol, Atenolol, Nadolol
Used for acute coronary syndrome, CHF, and HTN
First generaion (nonselecive) beta blockers (e.g. propranolol) block both beta 1 and beta 2
receptors
Second-generaion (cardioselecive) beta blockers (e.g. metoprolol) produces selecive blockade
of beta 1 receptors (at usual doses)

Third-generaion (vasodilaing) beta blockers (e.g. Carvedilol) act on blood vessels to cause
dilaion but may produce nonselecive or cardioselecive beta blockade
Efects of Beta Blockers:
Decreased heart rate; if pt. has pulse less than 60, hold dose and contact provider
Decreased force of cardiac contracion (decrease contracility)
Decreased cardiac output
Slowed conducion through the AV node (for this reason, used to tx tachyarrhythmias)
Decreased BP
Bronchoconstricion (efects especially noted in those with asthma, COPD)
Less efecive metabolism of glucose when needed by the body (especially seen with folks taking
anidiabeic agents with beta blockers). These folks may experience prolonged hypoglycemia and
early signs of hypoglycemia such as tachycardia may be delayed thus delaying the recogniion of
hypoglycemia. Need to adjust diabetes meds.
Indicaions:
Primarily cardiac problems:
oAngina
oHypertension
oTachyarrhythmias
oMI (may help prevent reinfarcion & arrhythmias)
oglaucoma (by decreasing intraocular pressure)
Contraindicaions:
oBradycardia
oheart blocks
oacute decompensated CHF (pt. presening to the ED will luid overload and pulmonary
congesion; use with cauion; wait unil diureics have taken their efect; start on “ity
bity” doses and then increase)
oAsthma (b/c of bronchoconstricion)
oOther pulmonary problems with bronchoconstricion such as COPD
Speciic Beta Blocker Drugs:
Metabolized in liver, excreted via kidneys
Prototype: Propranolol (Inderal)
Inderal is the oldest beta blocker
Non-Selecive: blocks both beta 1 (cardiac) and beta 2 (smooth muscle in bronchi and blood
vessels)
Used for: HTN, arrhythmias, angina, MI, cardiomyopathies, pheochromocytoma,
hyperthyroidism (thyroid storm), prevenion of migraines
Cardio selecive Beta Blockers: more efects on Beta 1 than Beta 2 in theory.
oThe selecivity may be lost at higher drug doses because most organs have both receptor
sites
oDrugs in this category include:
•Atenolol (tenormin): HTN, angina, MI;
•Esmolol (brevibloc): arrythmias (tachyarrythmias)
•Metoprolol (lopressor): HTN, MI
Beta Blockers that effect Alpha 1 and Beta 1,2
Some block alpha 1 (cause vasodilaion)

Some block beta 1 and beta 2 receptors (all non-selecive efects)
Less bradycardia and less tachycardia than other vasodilators
Example: Labetalol (Normodyne): used in HTN, Hypertensive emergencies causes less
bradycardia than other drugs
General Information (Beta Blockers)
Do not stop abruptly: May cause a rebound hypertension, may cause or aggravate angina; risk of
arrhythmias; may cause bradycardia; may cause impotence in men (common SE)
Instead taper over 1-2 weeks
Treaing adverse efects of beta blockers:
oatropine for bradycardia (if profound)
odigoxin and diureics for CHF (to treat volume issues)
obronchodilators for bronchoconstricion
Usually stopped before surgery due to the fact myocardial depressants are increased by general
anesthesia
Doses may need to be decreased in renal or hepaic disease
Beta blockers alone generally not efecive in Blacks; this is b/c they have low levels of renin and
b/c Beta blockers have to reduce renin in order to work. A muli-drug regimen is required
Asians usually need smaller doses than whites
Adverse efects are more common in the and may need to be elderly doses smaller
Educate paients well: paient may experience faigue and dizziness and oten quit taking them;
they oten quit taking them because they feel awful the irst few weeks; this usually subside in a
few weeks.
Cholinergic Drugs
Parasympathomimeics- simulates PNS
Cholinomimeics- similar to acetylcholine
Simulate the PNS the same way acetylcholine does
Efects of drugs last longer than endogenous acetylcholine
Efects of cholinergic drugs:
Decreased HR
Vasodilaion
Increased tone and contracility of GI smooth muscle, relaxaion of GI sphincters and increased
GI secreions
Increased tone and contracility of smooth muscle of the bladder and relaxaion of bladder
sphincter
Increased tone and contracility of bronchial smooth muscle
Increased respiratory secreions
Pupil constricion
Cholinergics: contraindicaions-not all of these are absolute contraindicaions
Urinary obstrucion
GI obstrucion
Asthma (they increase secreions; that could be bad)
Pepic Ulcer Disease (PUD)
Coronary Artery Disease (CAD)

Hyperthyroidism-if you give this drug to a hyperthyroidism pt. you would see an increase in HR,
iniial response is bradycardia, baroreceptors are simulated and over compensate, p 175;
aggravaion of their tachycardia
Indicaions:
Myasthenia Gravis: an autoimmune disease where acetylcholine receptors are destroyed
resuling in muscle weakness to try to increase the levels of acetylcholine
oTreated with: Neosigmine (prosigmin) which is the prototype drug for this category
oDrugs used in the treatment of myasthenia gravis include Mesinon, Prosigmine and
Tensilon. Paients who have undergone surgery may also sufer from muscle weakness as
result of anestheic drugs that were administered. Under these circumstances, the same
set of drugs used to treat myasthenia gravis can be used as well.
Glaucoma is another condiion where cholinergic drugs are used to help reduce the pressure
inside the eye.
oHumorsol and Phospholine Iodide are a few of the drugs used to treat glaucoma
paients.
Anidote to cholinergic drugs
Atropine: used as the anidote in a cholinergic overdose situaion; can also be used in
bradycardia b/c it also increases HR
Signs and symptoms of a cholinergic overdose (cholinergic crisis) include: abdominal cramps,
diarrhea, excessive mouth secreions, diiculty breathing, muscle weakness
Some herbal drugs have been seen to simulate cholinergic receptors and cause cholinergic crisis
Ileus (bowel goes to sleep with limited mobility) –used to give Neosigmine to increase gut
moility
Anti-ch olinergic Drugs: Parasympathetic depressants
Cholinergic blockers
Parasympatholyic agents
Block the acion of acetylcholine on the PNS
Occupy receptor sites at the parasympatheic nerve endings so fewer sites are free to respond
to acetylcholine
Efects of anicholinergic drugs
Bronchodilaion
Decreased respiratory tract secreions
Acts as an anispasmodic on the GI tract (decrease tone and moility)
Pupil dilaion (mydriasis)
Decreased salivary and sweat gland secreions
Relaxaion of ureters, urinary bladder (decreases tone, thus may be used for control of mild
inconinence)
Relaxes smooth muscle in gallbladder and bile ducts
Indicaions of anicholinergic drugs
Pre-op: to prevent vagal simulaion and potenial bradycardia, hypotension and cardiac arrest
that can be seen with surgery
Prebronchosocsopy (bronchodilates, decreases secreions)
GI disorders (decreases secreions): divericuliis, ulceraive coliis
GU disorders (anispasmoic efects): anispasmodic efects, decrease frequency and pain of
urinaion

Ophthalmic efects: dilate pupil for eye exam
Respiratory disorders: asthma (used for bronchodilaion); beta 2 agonist are usually more
important in asthma
Parkinson’s Dx: decrease spasicity, tremors
Contraindicaions of anicholinergic drugs:
Prostaic hypertrophy
Glaucoma (increases ocular pressure)
Tachyarrhythmias
Myocardial infarcion-using tend to increase mortality
Congesive Heart Failure
Gastro-Esophageal relux disease—b/c of changes in secreion
Anicholinergic: speciic drugs:
Atropine: prototype drug
oWorks by prevening endogenous acetylcholine from acivaing its receptor
oUsed to treat bradycardia and asystole by blocking the PNS’s atempt to slow the heart
oUsed pre-op, in inhalaion form (nebulizer) for asthma)
Scopolamine:
oMoion sickness (PO or transdermal patch)
oCauses drowsiness (b/c of CNS simulaion), relaxaion if given pre-op
oCauses pupil dilaion and couldn’t read up close
Ditropan (oxybutynin):
Decreases bladder spasms and decreases frequency
Anticholinergic: General info
Anidote for an overdose is phyosigmine salicylate (Anilirium)
Anidepressants, anihistamines and anipsychoic drugs and OTC sleeping pills have
anicholinergic efects. DON’T TAKE TOGETHER
Anicholinergic drugs decrease a pt.’s ability to sweat; this increases the risk of heat stroke and
exhausion (elderly and really young are at greatest risk for this)
SE: dry mouth increased dental caries & tooth loss due to decrease in saliva producion,
consipaion due to decreased GI moility; saliva helps to protect our teeth
Elderly: SE are more prevalent, blurred vision, confusion, heat stroke, consipaion, urinary
retenion, hallucinaions and other psychoic efects
You have been assigned to teach 14-year-old Maria and her parents about the use of
epinephrine to treat Maria’s bee sing reacions. Maria is a paient in a pediatrician’s oice,
where you are atending a clinical rotaion. She had an anaphylacic reacion yesterday. Her
parents took her to the emergency department, where she received iniial treatment, and then
she and her parents were instructed in the use of the epinephrine pen (EpiPen). The parents tell
you, “They told us about this pen, but we were so upset with all that went on, we really don’t
understand why Maria needs to use this medicaion.” Your teaching will focus on knowledge of
the use of epinephrine in the treatment of anaphylaxis.
CRITICAL THINKING CASE 1
1. What informaion should you provide to the family regarding inspecion of the epinephrine pen?
Soluion turns brown or precipitate forms, don’t use
2. The parents tell you that they don’t understand why Maria’s heart rate was so rapid ater she
was treated with epinephrine in the emergency department. The mother says, “I don’t know

whether she should get that drug again. Her heart rate got really high. The nurse told us that was
OK; what do you think?” explain that heart rate is rapid b/c of epinephrine simulates heart to
contract at a higher rate and intensity
3. Maria’s father says, “Why did she have such a hard ime breathing ater the sing?” chemicals that
were released in the allergic reacion (i.e. histamine) caused bronchoconstricion
Other informaion to know:
Single use delivery device, IM injecion, need to be over 66 lb (there is an epi-pen jr. for 33-66 Lbs.),
typically a pt. will have 2 pens; storage: sensiive to heat and light; store at room temp in dark place.
Check expiraion date; always carry with them; if she develops similar symptoms again, needs to self-
administer; contains 2 ml, so there will be some epinephrine let in the device ater admin; need to
get immediate medical atenion b/c short-lived relief; rxn can be biphasic; epi can cause
tachycardia, sweaing, nervousness.
CRITICAL THINKING CASE 2
You are working with Mr. J., who is scheduled to have a knee replacement surgery this morning. You
cannot ind history and physical on his chart. You read the preoperaive orders, which consist of muliple
drugs including atropine sulfate.
Atropine:
Anicholinergic=muscarinic blocker
MOA: Produces efects through compeiive blockade at muscarinic receptors
Efects: increases HR, decreases secreion from exocrine glands (salivary, bronchial, sweat, and
acid-secreing stomach cells), relaxaion of the bronchi, decreased tone of the urinary bladder
detrusor and decreased tone and moility of the GI tract; dilaion of the pupil (mydriasis), mild
CNS excitaion
Uses: preanestheic medicaion, eye disorders, bradycardia, intesinal
hypertonicity/hypermoility, and muscarinic agonist poisoning, pepic ulcer disease, asthma,
biliary colic.
Adverse efects: Xerostomia (dry mouth), blurred vision and photophobia, elevaion of
intraocular pressure, urinary retenion, consipaion, anhidrosis (absence/deiciency of sweat),
tachycardia, asthma
Contraindicaions: glaucoma (b/c of increase intraocular pressure), intesinal atony, urinary tract
obstrucion, and tachycardia; use cauion with asthmaics
1. Why is it important that you obtain a history on Mr. J before administering the atropine? Don’t
want to give atropine to pt. with myasthenia gravis; can increase muscle weakness from lack of
acetylcholine receptors.
2. Shortly ater you administer the atropine, Mr. J starts to hallucinate. He states he must run away
from the man chasing him. He is delirious, and his skin is hot, dry and lushed. You turn the lights on
to assess him beter and he complains the light hurts his eyes. What acion should you take?
Stop the drug immediately.
Difereniate drug toxicity from psychosis. At therapeuic doses atropine can cause mild
CNS excitaion. Toxic doses can cause hallucinaions and delirium, which can resemble
psychosis. Extremely high doses can result in coma, respiratory arrest, and death.
Administraion of acivated charcoal to adsorb drug or physosigmine (an inhibitor of
acetylcholinesterase) may be indicated based on severity
Mr. J has been assigned to your care as part of your clinical session, which is scheduled for the next
morning. Your clinical instructor has asked you to be prepared to discuss the adverse efects of a new

medicaion that has been ordered for Mr. J, as well as the nursing responsibiliies associated with these
adverse efects. The drug is propranolol (Inderal). What informaion should you be prepared to discuss
with your instructor?
Propranolol
is the prototype for irst gen (nonselecive; beta 1 and beta 2) beta blocker
efects: decreases force of ventricular contracion, and suppress impulse conducion through
the AV node, suppresses secreion of renin (by blocking beta 1); by blocking beta ,
2
Propranolol causes: Bronchoconstricion, vasoconstricion, and reduced glycogenolysis
indicaions: HTN, angina pectoris, cardiac dysrhythmias, and MI; addiion indicaions:
migraines and stage fright
adverse efects: bradycardia, AV heart block, HF, rebound HA (with abrupt withdrawal),
bronchoconstricion (hazardous to asthmaics); inhibiion of glycogenolysis (dangerous in
DM), CNS efects (depression, insomnia, nightmares and hallucinaion)
Precauions/contraindicaions: severe allergy, DM, cardiac, respiratory, and psychiatric
disorders
Interacions: calcium channel blockers (combinaion may cause excessive
cardiosuppression); insulin (propranolol can impede early recogniion of insulin induced-
hypoglycemia, which is manifested as tachycardia. In addiion, propranolol can block
glycogenolysis, the body’s mechanism for correcing hypoglycemia).
Nursing indicaions
Warn against abrupt disconinuaion, which can cause tachycardia and ventricular
dysrhythmias; advise carrying adequate medicaion on trips
Advise monitoring of blood pressure and HR daily
Advise recording the incidence, circumstances, and severity of angina atacks
Monitor for improvement in ECG
Hold drug is HR <60bpm
Heart failure can be an adverse efect of this drug; inform pt about early signs of HR (SOB,
night coughs, swelling of the extremiies) and instruct to noify provider if these occur
Can also cause postural hypotension: inform pt about signs of hypotension (light-
headedness, dizziness); advise them to sit or lie down if these develop. Advise him to move
slowly if changing posiion.
If pt. is an asthmaic or diabeic, consult provider for a cardioselecive beta blocker
If this pt. is a diabeic, warn him that tachycardia cannot be relied on as an indicator of
hypoglycemia; teach him to recognize sweaing, hunger, faigue, poor concentraion as signs
of hypoglycemia
Insulin dose may need to be reduced b/c of blocking of glycogenolysis
Chapter 20 intro to the CNS
CNS
Has at least 21 neurotransmiters (e.g. dopamine, NE, serotonin, enkephalins)
Blood brain barrier: allows lipid soluble drugs and drugs that are able to use a transport system
to cross; protein-bound and highly ionized drugs cannot pass; not fully developed at birth

Adaptaion of the CNS to prolonged Drug exposure: increased therapeuic efect, decreased SE,
tolerance, and physical dependence
Pain lecture/chapter 28
Analgesics –drugs that relieve pain w/o causing loss of consciousness
Opioid-any drug, natural or syntheic, that has acions similar to those of morphine
oPure opioid agonists: acivate Mu and kappa receptors; produce analgesia, euphoria,
sedaion, respiratory depression, physical dependence, consipaion; two groups:
Strong opioid agonists: morphine is the prototype
Moderate to strong opioid agonists: Codeine is the prototype
oAgonist-antagonist opioids: four available= pentazocine, Nalbuphine, Butorphanol, and
buprenorphine; produce analgesia when given alone and antagonize analgesia caused by
pure opioid agonists; have a ceiling to their analgesic efects.
oPure opioid antagonist: act as antagonists at mu and kappa receptors; do not produce
analgesia or any of the other efects caused by opioid agonists; used to reverse
respiratory and CNS depression caused by overdose with opioid agonists;
methylnaltrexone is used to treat opioid-induced consipaion; Naloxone [Narcan] is the
prototype for the pure opioid antagonists.
Opiate-more speciic, applies only to compounds present in opium (e.g. morphine, codeine)
Narcoic-used to mean an analgesic, a CNS depressant, and any drug capable of causing physical
dependency (legal sense; used to refer to opioids and marijuana, cocaine, LSD); less preferred
term
3 families of pepides with opioid-like properies: enkaphalins, endorphins, and dynorphins;
serve as neurotransmiters, neurohormones, and neuromodulators; found in CNS and peripheral
issue
3 main classes of opioid receptors: mu, kappa, and delta
oEndogenous opioid pepides afect all of these receptors
oMu-most important pharmacologically; acivaion of Mu receptors causes: analgesia,
respiratory depression, sedaion, euphoria, physical dependence, and decreased GI
moility
oKappa-acivaion causes: analgesia, sedaion, and decreased GI moility; efected by
Dilaudid
oDelta-not afected by opioid analgesics currently created
oDrugs have been created to mimic endogenous opioid pepides
Nocicepive pain:
comes from simuli from somaic (musculoskeletal) or visceral structures (internal organs);
simuli comes from injury to either of these
Responds well to opioid analgesics
Neuropathic pain
Simuli abnormally processed by the CNS
Oten results from poorly managed nocicepive pain
Many imes pt. with chronic nocicepive pain can develop neuropathic pain
Diabeic paients with diabeic neuropathies.
Doesn’t respond well to opioid neuropathic analgesics
Ani-seizure drugs (gavapenin) can halt neuropathic pain: chap 20
Drugs for treating cancer patient’s pain
Opioids are the most efecive analgesics available and the primary drugs for treaing moderate
to severe cancer pain; relieve pain in 90% of cases
Pure opioid agonists are preferred to the agonist-antagonists; if pain is not too intense, a
moderately strong opioid (oxycodone) is appropriate; if pain is severe, use a strong opioid
(morphine)
In general, meperidine (pure opioid agonist), and agonists-antagonists (buprenorphine,
Butorphanol, nalbuphine, and pentazocine) should be avoided meperidine can only be used for a
few days before a toxic metabolite accumulates, and agonists-antagonists are less efecive than
pure opioid agonists and if given to a pt who is physically dependent on pure opioid agonist, can
prevent pure opioid agonist from working and precipitate withdrawal
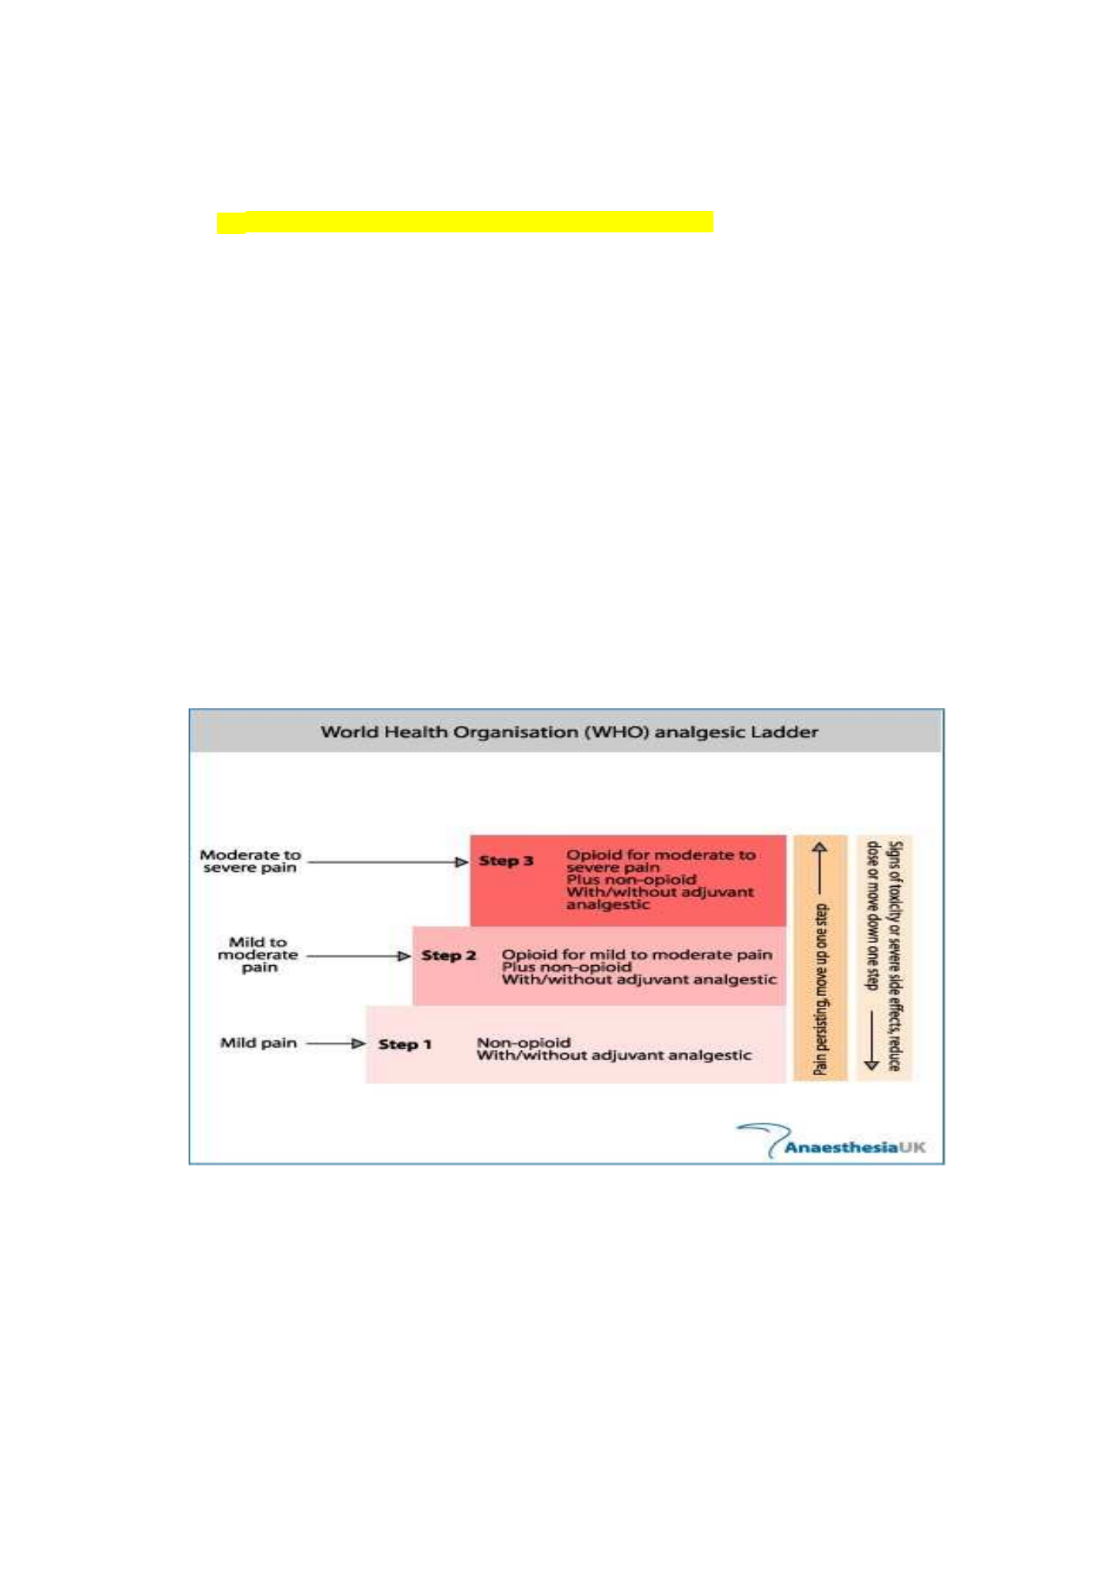
The WHO analgesic ladder for CA pain:
Mild to moderate pain—First step is nonopioid analgesics: NASIADs and acetaminophen
More severe pain—second step adds opioids of moderate strength (oxycodone, hydrocodone);
thus: opioid + nonopioid
Severe pain—the top step subsitutes powerful opioids (i.e. pure opioid such as morphine,
fentanyl; Dilaudid) for the weaker ones
Adjuvant analgesics, which are esp. efecive against neuropathic pain, can be used on any step
of the ladder (amitriptyline, carbamazepine, dextroamphetamine)
Seven Principles for treating CA pain

1. Perform a comprehensive pretreatment assessment to idenify pain intensity and the underlying
cause
2. Individualize the treatment plan
3. Use the WHO analgesic ladder and NCCN guidelines to guide drug selecion
a. NCCN guidelines: using the numeric scale, pain report of 1-3 Tx begins with nonopioid;
4-10 Tx should start with a opioid
4. Use oral therapy whenever possible
5. Avoid IM injecions whenever possible
6. For persistent pain, administer analgesics on a ixed schedule around the clock (ATC), and
provide addiional rescue doses of a short-acing agent if breakthrough pain occurs
7. Evaluate the pt. frequently for pain relief and drug side efects
Tolerance, Addiction, and Physical Dependence
Tolerance- gradually takes more to achieve the same physiological efects; a state in which a
speciic dose produces a smaller efect than it could when treatment began; dosage must be
increased to maintain the desired response; in cancer pt. need for greater dose doesn’t
necessarily represent the development of tolerance; more likely a sign that pain is geing worse
due to disease progression; opioid tolerance develops to analgesia, euphoria, respiratory
depression, and sedaion, not consipaion; EVERY PT. ON OPIOIDS WILL EVENTUALLY DEVELOP
TOLERANCE
Cross tolerance-when one opioid confers a similar degree of tolerance to all others
Addicion-a disease process characterized by coninued use of a psychoacive substance despite
physical, psychologic, or social harm; although it rarely occurs, fears about this are a major cause
of undertreatment; a pt. cannot become addicted to a drug if they truly have pain, the process
of addicion cannot be acivated
Psychologic dependence-major underlying cause of addicion
Physical Dependence-a state in which an absinence syndrome (unpleasant but not dangerous)
will occur if a drug is abruptly withdrawn; intensity and duraion determined by duraion of drug
use and half-life of the drug; can be minimized by slow withdrawal of drug; NOT THE SAME AS
ADDICTION; withdrawal (tachycardia, increased pain, changes in respiratory rate when opioid is
removed)
Pain intensi ty scales
Valuable for assessing pain and for seing pain relief goals and evaluaing Tx
Descripive and numeric scales are used for adults and pain afect FACES scale is used for young
children and for cogniively impaired pts
For the Wong Baker FACES scale, explain to the pt that the irst face represents a person who
feels happy b/c he or she has no pain, and that the other faces represent people who feel sad
b/c they have pain, ranging from a litle to a lot. Explain that face 10 represents a person who
hurts as much as you can imagine, but that you don’t have to be crying to feel this bad. Ask the
pt to choose the face that best relects how he or she is feeling. The numbers below the faces
correspond to the values in the numeric pain scale shown in the igure below
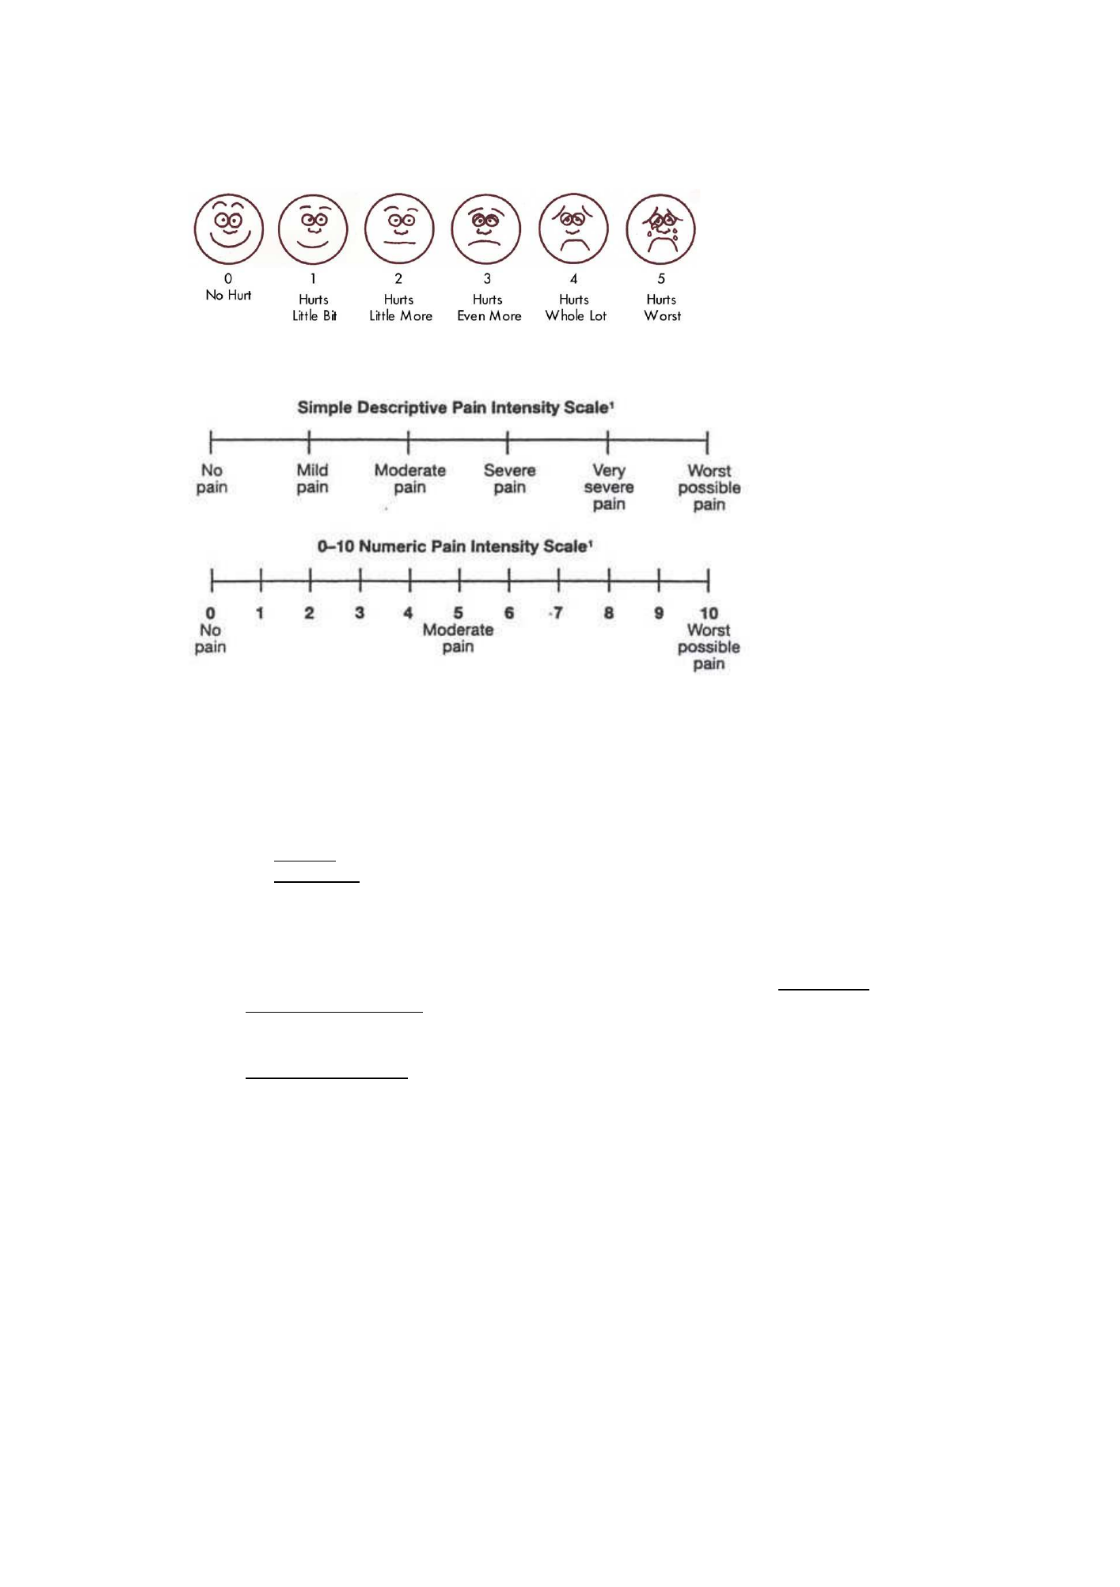
For verbal adults:
Opioid Analgesics
Opioid analgesics do not have a ceiling dose; start with usual dose and may need to work way up
as the paient takes med overime
Divided into two groups
1. Agonists
2. Antagonists
Morphine-like agonist
Act centrally
Bind to receptors in the brain and SC where they acivate the descending inhibitory pathways
These receptors are the binding sites for endogenous pain relievers such as endorphins,
enkephalins, dynorphins
When a drug binds to these receptors, pain relief is experienced
When a drug acts as an antagonist to these sites, pain relief and any side efects are blocked (i.e.
respiratory depression)
General information:

Anyone receiving a full mu agonist should not receive an agonist-antagonist because the efects
of the original opioid will be reversed and withdrawal may be precipitated
The ideal pain relieving agent is a potent analgesic devoid of side efects but the ideal agent does
not exist.
General information: Mu agonists
Mu agonists are beter at managing as opposed to nocicepive pain neuropathic pain (but are
useful in all types of pain)
Mu agonists are used in combinaion with other pain relievers such as Tylenol and NSAIDS for
addiive efects.
Given via several routes: PO, transdermal, IV, PCA, epidural and IM
Typically classiied as schedule 2 or 3 drugs
Side efects may include drowsiness (may allow paient to sleep ), slowed GI despite pain
moility, N/V, mental clouding, pupil constricion, and respiratory depression)
SE occur mostly in opioid naïve paients and decrease in occurrence as the body develops
tolerance for the drug ater a few days
Morphine Sulfate: the prototype
No doseceiling
Titrate as needed
General rule of thumb: give q 2-4 hours and if the previous dose did not achieve the pain relief
goal, then the next dose should be increased by 25-50%
Consider the use of addiive drugs as well
Morphine Sulfate: the prototype
A few indicaions:
1. Moderate to severe acute pain (7 or >/10)
2.Chronic pain (cancer)
3. Post-op pain management
4. Acute pulmonary edema and MI (helps relieve pulmonary congesion, lowers myocardial
oxygen demands and vasodilates)
Contraindicaions or cauious use:
1. Respiratory depression
2. Lung disease (i.e. asthma)
3. Liver or kidney disease
4. increased ICP
5. Hypersensiivity
6. decreased LOC
7. Hypotension
Routes include: PO, PO (controlled release), IM, SQ, transdermal patch, IV/PCA, epidural,
intrathecal, rectal
Side Efects: (with standard dose): consipaion, increased ICP, orthostaic hypotension, urinary
retenion, N/V, mental clouding, sedaion
With overdose: respiratory depression, coma, hypotension, pinpoint pupils, death
Note: doses and responses are highly individual, Start Low, Go Slow (especially with the elderly)

Fentanyl (Sublimaze):
Potent
Short duraion of acion
Quick onset (within 1-2 minutes)
Good for procedural pain when given IV (i.e. colonoscopy)
The transdermal form (Duragesic) is used in the treatment of . (absorbed slowly: chronic pain
onset 12-24 hours but lasts 3 days)
Hydromorphone: (Dilaudid)
Semi-syntheic derivaive of morphine
Same acions, uses, contraindicaions, and adverse efects of morphine
More potent on a milligram per milligram basis (doses are typically SMALLER)
Check equianalgesic table, 308
Equianalgesic doses of pure opioid agonists and tramadol
Equianalgesic dose=dose that will produce the same degree of analgesia as 10 mg of parenteral
morphine
Agents for moderate to
severe pain
parenteral PO Duraion (hours)
Morphine 10 mg 30 mg 3-4
hydromorphone 1.5 mg 7.5 mg
Codeine:
Naturally occurring opioid used for mild to moderate pain control and for cough
More efecive when given orally than many other opioids and less likely to lead to dependence
Oten combined with ASA or Tylenol
Hydrocodone:
Similar to codeine
Used in combinaion Hycodan for cough
Used with Tylenol for pain (Lortab, Vicodin)
Oxycodone (Oxyco ntin)
Semi-syntheic derivaive of codeine
For moderate to severe pain
Available alone (Roxicodone, Oxy-IR), Oxyconin)
With ASA (Percodan)
With Tylenol (Percocet)
Meperidine (Demerol)
Syntheic similar to morphine
AVOID THIS AGENT!!!!!!
PO is only half as efecive as parenteral because of irst pass efect
Requires more frequent administraion than morphine (shorter duraion than MS)

A metabolite called normeperidine accumulates and causes CNS simulaion, confusion, tremors,
hallucinaions, agitaion, seizures.
Normeperidine has a half-life of 15-20 hours compared to meperidine’s 3 hours.
An antagonist works against the meperidine NOT the normeperidine
Poor choice especially for the elderly
Normeperidine is excreted through the kidneys
o thus, don’t use Demerol if paient has renal insuiciency
oPoor choice for sickle cell (most have renal insuiciency)
More likely to cause delirium than any other opioid in post-op paients
It is NOT true that Phenergan given with Demerol poteniates the Demerol
oPhenergan is a poor choice with Demerol because of addiive side efects: resp.
depression, increased sedaion, hypotension and also lowers the seizure threshold
Agonists-Antagonists
Have at some receptor sites and agonist acivity antagonist acivity at other sites (mixed
agonist-antangonist)
Have a to analgesia which is quickly reachedceiling
Not recommended as a irst line drug for any type of pain
Many believe that these drugs don’t cause respiratory depression BUT in equianalgesic doses
the risk for respiratory depression is the same
If given to a paient on a mu opioid, will cause reversal of pain relief and withdrawal symptoms
of those with an opiate dependence
Some examples of agonists-antagonists:
Nalbuphine (Nubain)
Only given parenterally
Someimes given in MI (does not cause cardiac efects such as hypotension)
At equianalgesic doses Nubain and Morphine produce a similar degree of respiratory depression
Very sedaing
At about 30 mg. ceiling efect is achieved
Low abuse potenial, thus not regulated by the “schedules”
Full opioid Antagonists
Reverse the analgesic and depressant efects of narcoic agonists by displacing the agonists from
their receptors
They have a shorter duraion than opioids so they may need to be repeated
Ex: Naloxone (Narcan)
Naloxone (Narcan):
Adult dose 0.4 mg IV
duraion is about one hour
Few adverse efects
Giving too much too quickly can precipitate severe pain that is diicult to control

Giving too much too quickly will: increase sympatheic acivity leading to hypertension,
tachycardia, arrhythmias, pulmonary edema, and cardiac arrest
General Points:
Believe your paient’s pain raing
Free yourself from bias regarding pain management
Be a paient advocate for pain management
Reassess pain regularly
Give pain meds around the clock not PRN
Avoid Meperidine (Demerol) and Darvocet (acetaminophen and propoxyphene; withdrawn from
market in 2010). Be able to explain the raionale to physicians
Don’t be afraid to use opioids in the elderly: Start Low, Go Slow
Avoid IM administraion
Use equianalgesic dosing
Uilize your resources: Pharm D, pain specialist, Clinical Pain Manual (McCafery and Pasero,
1999)
NSAIDS: (p. 889; chap 71)
Use: suppress inlammaion, pain relief reducion of fever
MOA: Inhibits cyclooxygenase (COX) the enzyme that converts arachidonic acid to
prostaglandins
COX1 vs COX 2:
oCOX 1: present in most issues, protects gastric mucosa, supports renal funcion, &
promotes platelet aggregaion.
oCOX2: present at the site of inlammaion where it mediates inlammaion and sensiizes
receptors to painful simuli
COX 1 inhibitors:
oGastric erosion and ulceraion
oBleeding tendencies
oAcute renal failure
oProtecion against MI’s (due to reduced platelet aggregaion)
COX 2 inhibitors:
oSuppression of inlammaion
oAlleviaion of pain
oReducion of fever
NSAIDS:
o1st generaion: inhibit cox 1 and 2
o2nd generaion: Cox 2 inhibitors
Contraindicaions:
oGastric erosion and ulceraion
oBleeding tendencies
oAcute renal failure
Side efects: GI efects, bleeding
NSAIDS: First Generation Agents (inhibi t COX 1 and COX 2)

Aspirin: most widely used, nonselecive inhibitor of COX; an irreversible COX inhibitor; highly protein
bound, excreted via the kidneys
Adverse efect: Reyes’s syndrome (encephalopathy and faty liver; mortality 20-30%); avoid use
of aspirin in children with chickenpox/inluenza for this reason
Reacions are seen more in folks with asthma, hay fever, chronic uricaria, nasal polyps
Avoid use with warfarins, glucocoricoids, alcohol
SE: innitus, dizziness, HA
Formulaions: Bufered (bufer included with pill to prevent elevaion of gastric pH); enteric
coated (dissolve in intesine rather than stomach); rectal suppositories (pt. who is NPO)
Stop ASA prior to surgery- Inhibits platelet aggregaion for the life of the platelet (7days)
Other examples:
ibuprofen, naproxen, arthrotec,fenoprofen
Toradol (ketorolac)- only IV NSAID available- ONLY USE FOR LESS THAN 5 DAYS SINCE RISK FOR
RENAL FAILURE
NSAIDS: Second Generation Agents (inhibit COX 2 only)
Celecoxib (Celebrex): prototype, relieves symptoms of arthriis, but causes less GI ulceraion and
bleeding than tradiional NSAIDS; protein binding is extensive (97%)
Indicated for RA & OA
May cause renal toxicity, dyspepsia, abd. pain
Rofecoxib (Vioxx): pulled from the market 10/04
Acetaminophen (Tylenol):
Not an NSAID; the only drug that inhibits cyclooxygenase but does not have aniinlammatory
properies
Use: anipyreic, pain relief. Similar to aspirin except the ani-inlammatory efects.
Adverse Efects: rare at therapeuic doses, doesn’t inhibit platelet aggregaion, no link to Reye’s
syndrome, overdose causes severe liver damage.
Overdose: avoid with alcohol,
Anidote: mucomyst
Gout Drugs
Gout: Allopurinol (Zyloprim)
MOA: reduces uric acid by inhibiing uric acid producion
USE: drug of choice for chronic gout, prevents tophus formaion, used prevent hyperuricemia
secondary to treatment of ani-cancer drugs
Adverse Efects:
–GI, N/V, diarrhea, abd. Discomfort, drowsiness, HA, metallic taste, long term use may
lead to cataract development
–Severe: hypersensiivity syndrome: fever, rash, eosinophilia, liver and kidney
dysfuncion, some may resolve spontaneously or require steroids, dialysis
Gout: Colchicine

MOA: anilammatory speciic for gout, not used for other types of inlammaion; speciic MOA
unknown
Use: treatment of acute gouty atacks, reduce the incidence of atacks in chronic gout, and
prevent an impending atack. IV or oral administraion, extravasaions can cause necrosis
Adverse efects: GI toxicity: N/V, diarrhea, abdominal pain, disconinue if/when GI symptoms
develop
0.5-1.2 mg iniially and then 1-2 hours unil pain relief or GI symptoms occur
Gout: Probenecid (Benemid)
MOA/uses: acts on the renal tubules to inhibit reabsorpion of uric acid promoing excreion of
uric acid and prevening formaion of new tophi, iniial treatment may induce episodes of gout,
may need other drugs added, prolongs the efects of penicillins and cephalosporins
Adverse Efects: GI, N/V, anorexia, take with food, hypersensiivity, kidney damage due to urate
deposits in the kidney, keep urine alkaline, force luids (2-3 L/day for the irst few days of
treatment)
Gout: Indomethacin (Indocin):
MOA: suppresses inlammaion (does not reduce hyperuricemia) (NSAID)
Use: treatment for acute gouty atacks
Adverse Efects: severe frontal HA, avoid with pepic ulcer disease, if used with probenecid
excreion is delayed; iniial dose is 50 mg then 25 mg 3-4 imes daily.
Migraines: (p. 319; chap 30)
Caused by inlammaion and dilaion of intracranial blood vessels.
oCGRP (calcitonin gene-related pepide): promotes migraine
oSeroinin (5-HT): suppresses migraines
Medicaions will intervene with these substances
General points: aniheadache drugs may be used to abort and ongoing atack or prevent an
atack from occurring; not all pts with a paricular type of HA respond to the same drugs
(individualized therapy is needed); several of the drugs employed may cause physical
dependence
Migraine: Abortive Thera py:
objecive is to eliminate the HA and suppress N/V
For mild to moderate s/s, aspirin-like analgesics are indicated:
oaspirin, Ibuprofen, acetaminophen, combinaion drugs (Tylenol/codeine)
oadjuncive therapy: metoclopramide (Reglan) to manage N/V, reverse gastric stasis
(improves ani-migraine drug absorpion)
oalso used in combinaion with cafeine and a barbiturate (iorinal)
oMidrin--combo drug containing acetaminophen, isometheptene (a sympathomomeic)
and a sedaive
oExcedrin Migraine—combo of Acetaminophen, ASA & cafeine:
For severe HA that don’t respond to irst-line medicaions use opioid analgesics:
oMeperidine (Demerol)—all the adverse efects of pure opioids

oButorphanol nasal spray (formerly available ad Stadol NS)—preferred
Migraine speciic drugs: ergot alkaloids and triptans:
Ergotamine: used to treat cluster headaches and as a irst-line drug to treat severe migraines
(aborive therarpy)
oMOA: unknown but thought to agonist acivity of serotonin receptors, promote vascular
constricion and reduce the amplitude of pulsaions
oAdverse Efects: N/V, weakness, numbness & ingling in the ingers and toes, angina,
tachycardia, bradycardia
oOverdose: ergoism (acute toxicity with Ergotamine); in addiion to the adverse efects
seen with the drug, can also see s/s of ischemia, cold, pale, numb extremiies, muscle
pain, gangrene. Those at higher risk: sepic paients, PVD, renal and liver impairment
oCan cause uterine contracions; should not be taken in pregnancy
Selecive serotonin-Receptor Agonist (“Triptans”)
oFirst line for moderate to severe migraines
oSumatriptan (Imitrex): prototype
oMOA: causes selecive simulaion of 5-HT receptors, causes vasoconstricion,
suppresses release of CGRT, suppresses release of neuropepides and decreases
perivascular inlammaion
oUse: abort on-going migraine atacks; associated symptoms are also managed
(photophobia, nausea)
oDosage: Oral (slow onset), nasal & sc (rapid onset)
oAdverse Efects: coronary vasospams are of most concern, chest pressure, heavy feeling
in arms, not related to ischemic heart disease (may be due to pulmonary
vasoconstricion), esophageal spasm, bronchoconstricion, intercostal muscle spasm,
oAvoid during pregnancy
oAvoid with use of ergot derivaives
oContraindicated in paients with previous MI, heart disease, or uncontrolled HTN
o Shouldn’t be combined with SSRIs or SNRIs b/c serotonin syndrome could occur
Other new agents of Migraine Aborive Therapy: other selecive serotonin receptor agonists
oNaratriptan (Amerge)
oRizatriptan (Maxalt)
oZolmitriptan (Zomig)
oAll are given PO
oAll acivate the 5-HT1 receptors with ulimate decrease in perivascular inlammaion and
intracranial vasoconstricion
Migraine: Prophylacic Therapy
oIndicated for those who have frequent atacks (2 or more a month), esp severe or don’t
respond to aborive therapy
oFrequent and severe episodes
oBeta-adrenergic blockers (propranolol, atenolol, metoprolol, imolol)
oDivalproex
oTricyclic anidepressants
oCalcium channel blockers
oEstrogen supplements can be used for menstrual associated migraine

Case Study I:
A 32 year old female is admited for 23 hour observaion for renal calculi. She self-reports a pain raing of
10/10. The staf is giving her the prescribed amount of morphine for several hours. She is also given
promethazine 12.5 mg. A short ime later, the nurse inds the paient unresponsive.
1. What do you think went wrong? Promethazine is a irst-gen, H1 receptor antagonist.
Promethazine can cause sedaion and severe respiratory depression. Morphine is also a CNS
depressant; the combinaion of these drugs can prove fatal since both caused respiratory
depression.
2. What other informaion do you need to make an adequate assessment? This pt.’s respiratory
rate/depth/degree of efort need to be assessed along with her HR, BP.
3. What recommendaions would you make in the management of this paient? This pt. needs
coninuous monitoring. There is no anidote for anihistamines, but naloxone, the morphine
anidote, may be indicated per physician’s order.
Case Study 2:
The paient is 24 hours status post C-Secion. The woman had her PCA pump disconinued at midnight
and she asked for pain medicaion at . The nurse administers 800 mg. At 6 am, the paient is4 am Motrin
sill experiencing pain. You are coming on duty and review the following pain orders for this paient:
Percocet 1-2 tablets q4-6 hr prn
Motrin 800 mg q6 hr prn
1. How would you have managed this paient? PCA pumps administer small doses of medicaion
(usually morphine); this paient should have been given another pain medicaion before she
began to complain of pain.
2. Write up a pain plan based on the physician orders as they are writen.
Case Study 3:
A 5 year-old child is status post emergency appendectomy. The surgeon has writen the following orders:
Demerol 50-75 mg IM q4-6 hr. prn
Tylenol 325 mg q 4-6 hr. prn
The nurse assesses the pain of the child using the Wong Baker Scale (faces). The child reports moderate
pain but does not want a shot. The nurse calls the surgeon to report her indings. The surgeon informs
the nurse that no addiional orders will be given. The nurse administers the Tylenol order around the
clock to manage the moderate pain.
1. Would you have managed this case diferently? If yes, how?
Explain fully
A shot is not necessary to treat a paient’s pain. The nurse can use the chain of command (staring with
the head nurse/huck) if the med order for Demerol needs to be changed to an PO route. Meperidine
(Demerol) used to be used as a irst-line medicaion for moderate to severe pain; however, it is falling out
of favor b/c of accumulaion of toxic metabolite (normeperidine). Acetaminophen can be used to treat
mild to moderate pain.

