


INFERTILITY
&
IVF

Def;
•Infertility – a year of regular unprotected intercourse without
conception
•Primary infertility – patient has never conceived
•Secondary infertility – indicates previous pregnancy but failure to
conceive subsequently
•Fecundability – probability of a cycle resulting in a pregnancy
•Fecundity – probability of a cycle resulting in a livebirth
•Subfertility – exhibits reduced reproductive efficiency

Factors Essential for Conception
•Healthy spermatozoa – deposited high in the vagina or near cervix –
changes to spermatozoa (capacitation, acrosome reaction and acquire
motility – motile spermatozoa (ascend through cervix – uterine cavity –
fallopian tube) – ovulation – patent tubes – fertilization at ampulla –
embryo reaching uterine cavity (after 3-4 days of fertilization) – receptive
endometrium for implantation – adequately functional corpus luteum

Physiological Infertility
•Anovulation – prior to puberty and after menopause
•Suppressive effect of hCG during pregnancy
•Relative infertility during lactation

Causes of Infertility
•Male factor – 30 – 40%
•Female factor – 40 – 55%
•Both – 10%
•Unexplained – 10%

MALE INFERTILITY
Pre-testicular
Endocrine
• Gonadotropin deficiency
• Obesity
• Thyroid dysfunction
• Hyperprolactinemia
Psychosexual
– Erectile dysfunction
– Impotence
•Drugs
•– Antihypertensives
•– Antipsychotics
•Genetic
•– 47 XXY (p. 229)
•– Y chromosome deletions
•– Single gene mutations

Testicular
Immotile cilia
(Kartagener) syndrome
• Cryptorchidism
• Infection (mumps orchitis)
• Toxins: Drugs, smoking,
radiation
• Varicocele
• Immunologic
• Sertoli-cell-only syndrome
• Primary testicular failure
• Oligoastheno-teratozoospermia

Post-testicular
Obstruction of efferent duct
• Congenital
– Absence of Vas deferens
(Cystic fibrosis)
– Young’s syndrome
• Acquired Infection:
Tuberculosis, Gonorrhea
• Surgical
– Herniorrhaphy • Vasectomy
Others
• Ejaculatory failure
• Retrograde ejaculation
• Hypospadias
• Bladder neck surgery
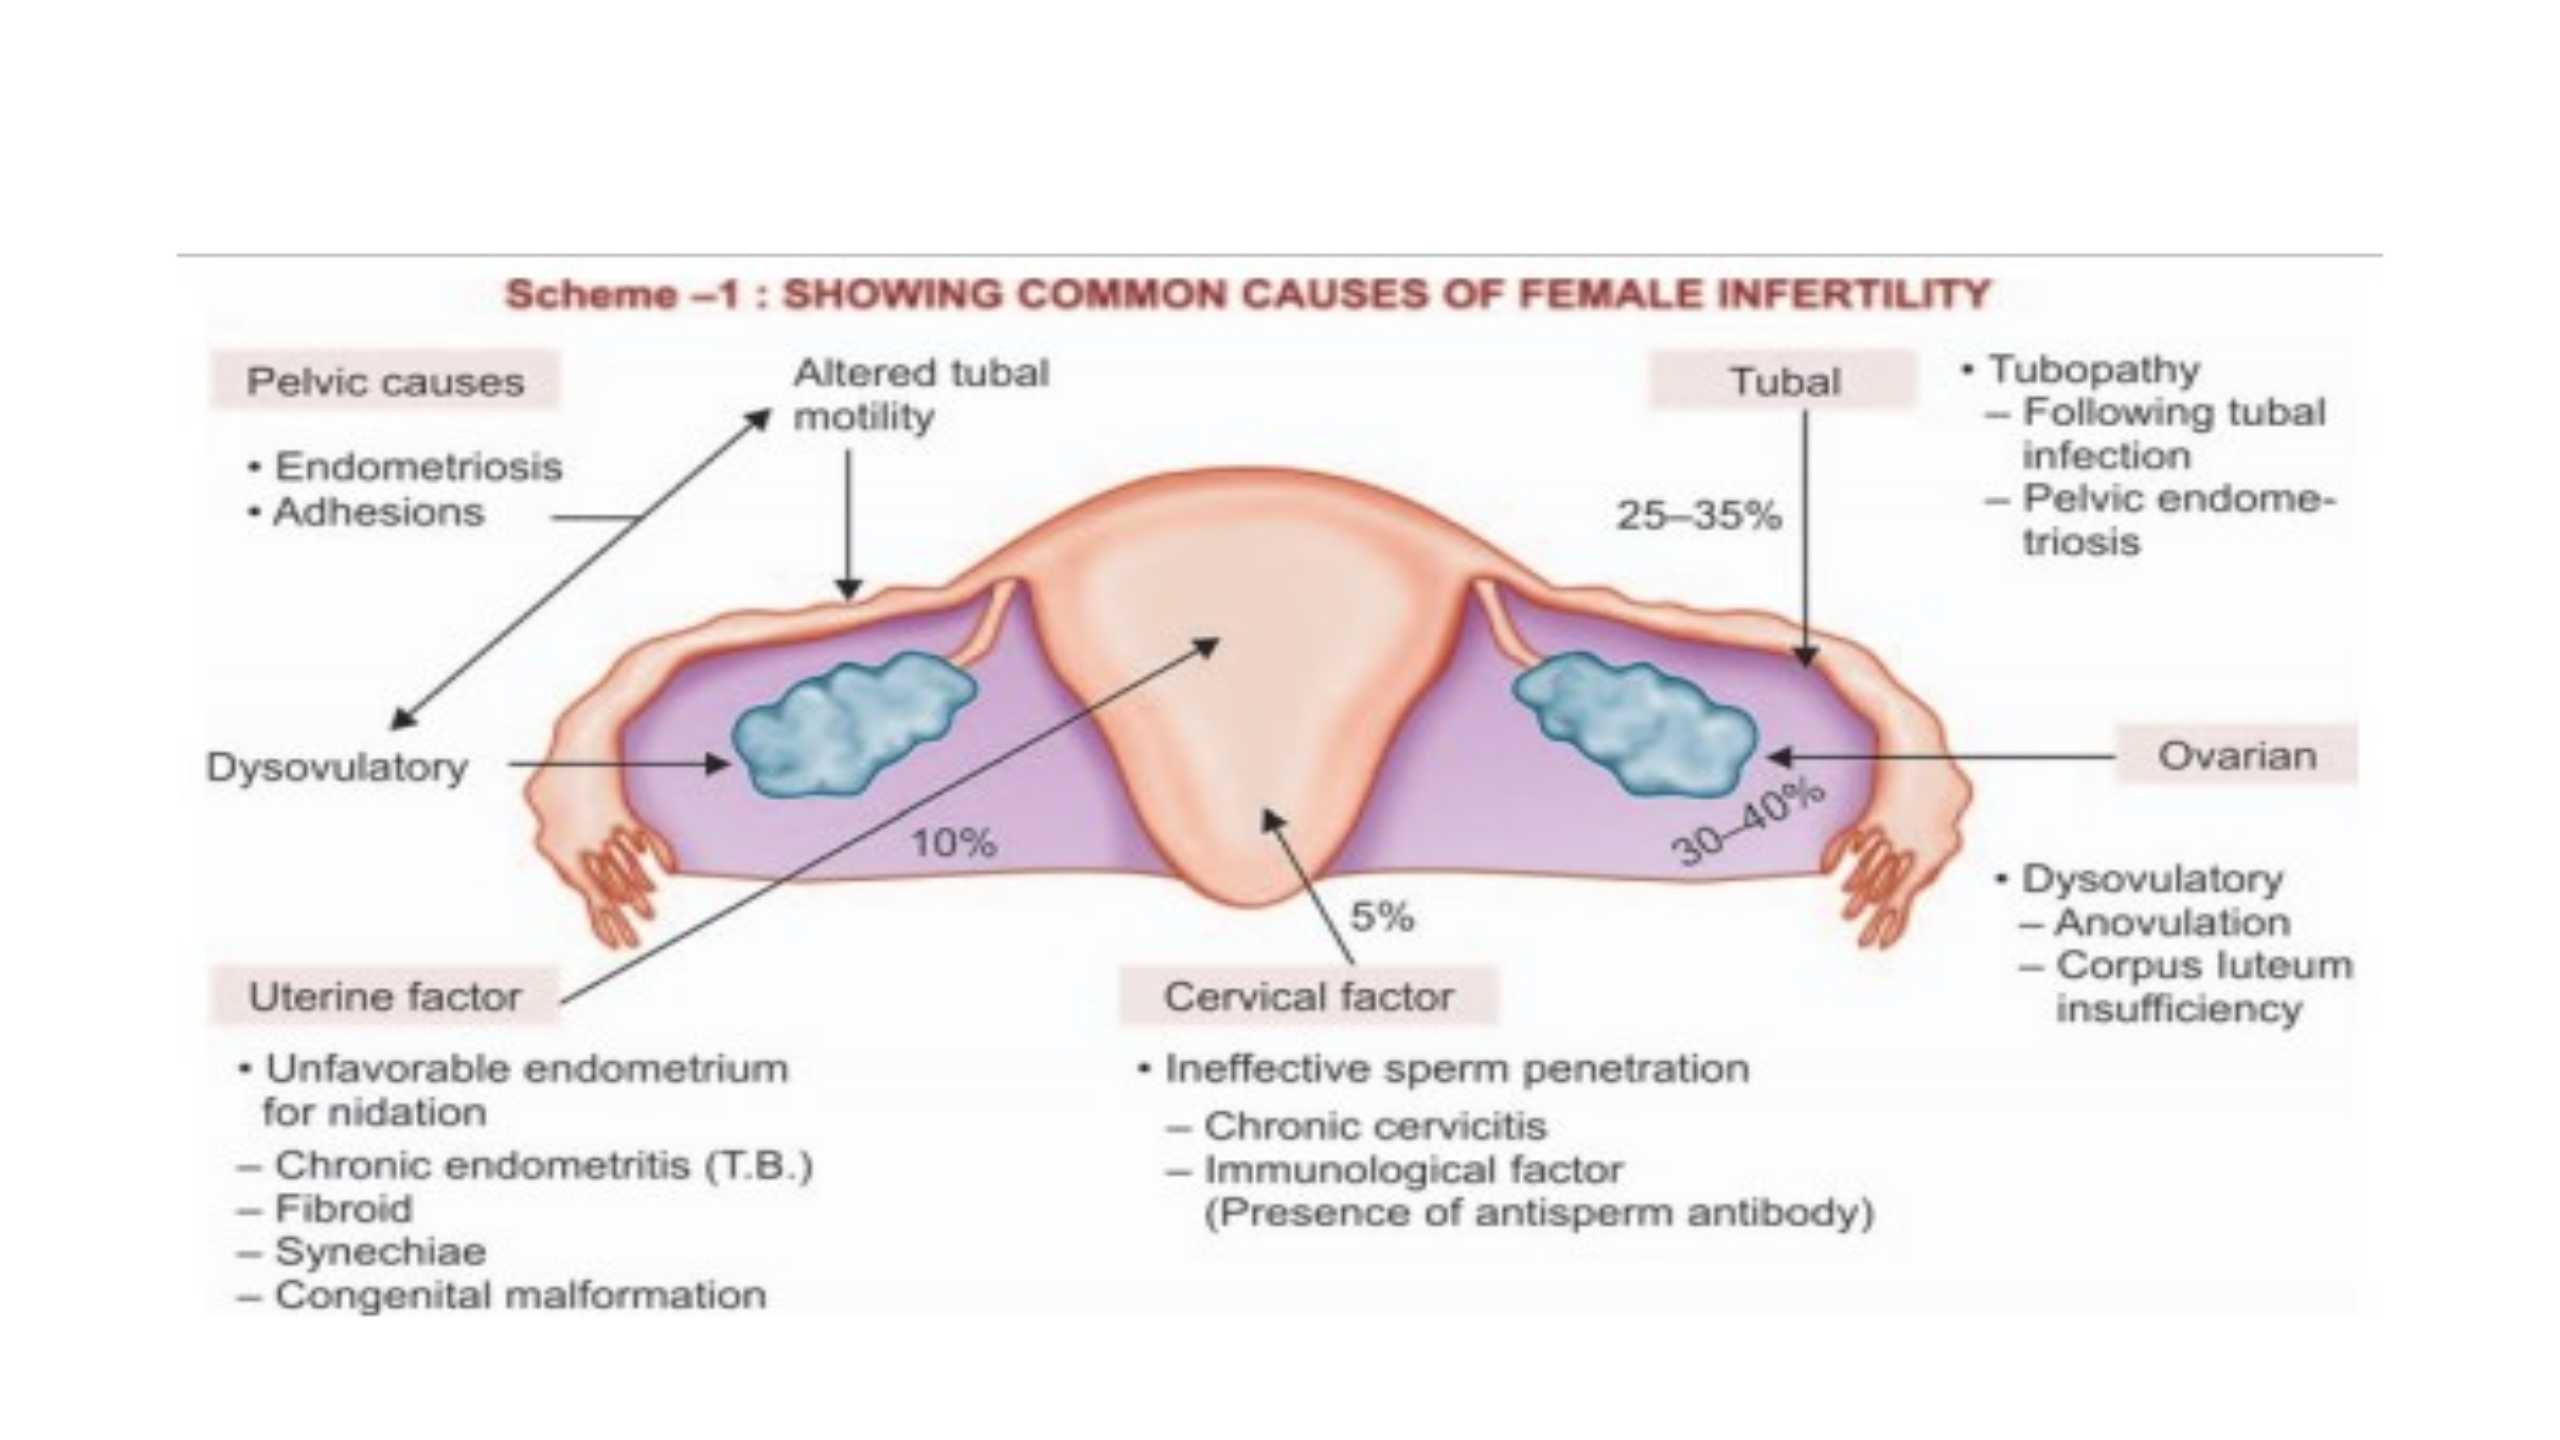
Scheme
-1:
SHOWING
COMMON
CAUSES
OF
FEMALE
INFERTILITY
Pelvic
causes
Altered
tubal
Tubal
*
Tubopathy
_
motility
"
_
Following
tubal
«
Endometriosis
infection
=
Pelvic
endome-
riosis
*
Adhesions
Dysovulatory
Ovarian
«
Dysovulatory
—
Anovula
tor
7
=
Corpus
luteum
Uterine
factor
Cervical
factor
insufficiency
:
Unfavorable
endometrium
*
Ineffective
sperm
penetration
for
nication
—
Chronic
cervicitis
-
Chronic
endometritis
(T.B.)
=
Immunological
factor
=
Fibroid
(Presence
of
antisperm
antibody)
-
Synechiae
=
Congenital
malformation
FEMALE INFERTILITY

Luteal Phase Defect (LPD)
•In this condition, there is inadequate growth and function of the
corpus luteum.
•There is inadequate progesterone secretion.
•The lifespan of corpus luteum is shortened to less than 10 days.
•As a result, there is inadequate secretory changes in the
endometrium which hinder implantation.
•LPD is due to defective folliculogenesis which again may be due to
varied reasons. Drug induced ovulation, decreased level of FSH and/or
LH, elevated prolactin, subclinical hypothyroidism, older women,
pelvic endometriosis, dysfunctional uterine bleeding

Combined factors
•General factors: Advanced age of
the wife beyond 35, aging
reduces the fertility in male also.
•Infrequent intercourse, lack of
knowledge of coital technique
and timing of coitus to utilize the
fertile period
•Apareunia and dyspareunia
•Anxiety and apprehension.
•Use of lubricants during
intercourse, which may be
spermicidal.
•Immunologic factors

CLINICAL APPROACH
•History
•Age / duration of marriage/ hx of previous smarriage / proven fertility
if any.
•A general medical history should be taken with special reference to;
•Female - tuberculosis, sexually transmitted disease, features
suggestive of pelvic inflammation or diabetes.
•Male - sexually transmitted diseases, mumps orchitis after puberty,
diabetes, recurrent chest infection or bronchiectasis.

•The surgical history should be directed especially towards abdominal
or pelvic surgery. This may be related to peritubal adhesions in
female, herniorrhaphy, operation on testes in males.
•Menstrual history
•Previous obstetric history
•Contraceptive practice
•Sexual problems

Examinations
•General examination
•Systemic examination - abnormalities like hypertension, organic heart
disease, chronic renal lesion, thyroid dysfunction, and other
endocrinopathies.
• Reproductive system includes— in males inspection and palpation of
the genitalia. Attention should be paid to the size and consistency of
the testicles.

•Gynecological examination includes
adequacy of hymenal opening,
evidences of vaginal infections,
cervical tear or chronic infection,
undue elongation of the cervix, uterine size, position and mobility,
presence of unilateral or bilateral adnexal masses—fixed or mobile
with or without tenderness and presence of nodules in the pouch of
Douglas.

•Speculum examination may reveal abnormal cervical discharge.
•The discharge is to be collected for Gram stain and culture

Special Investigations
•Males
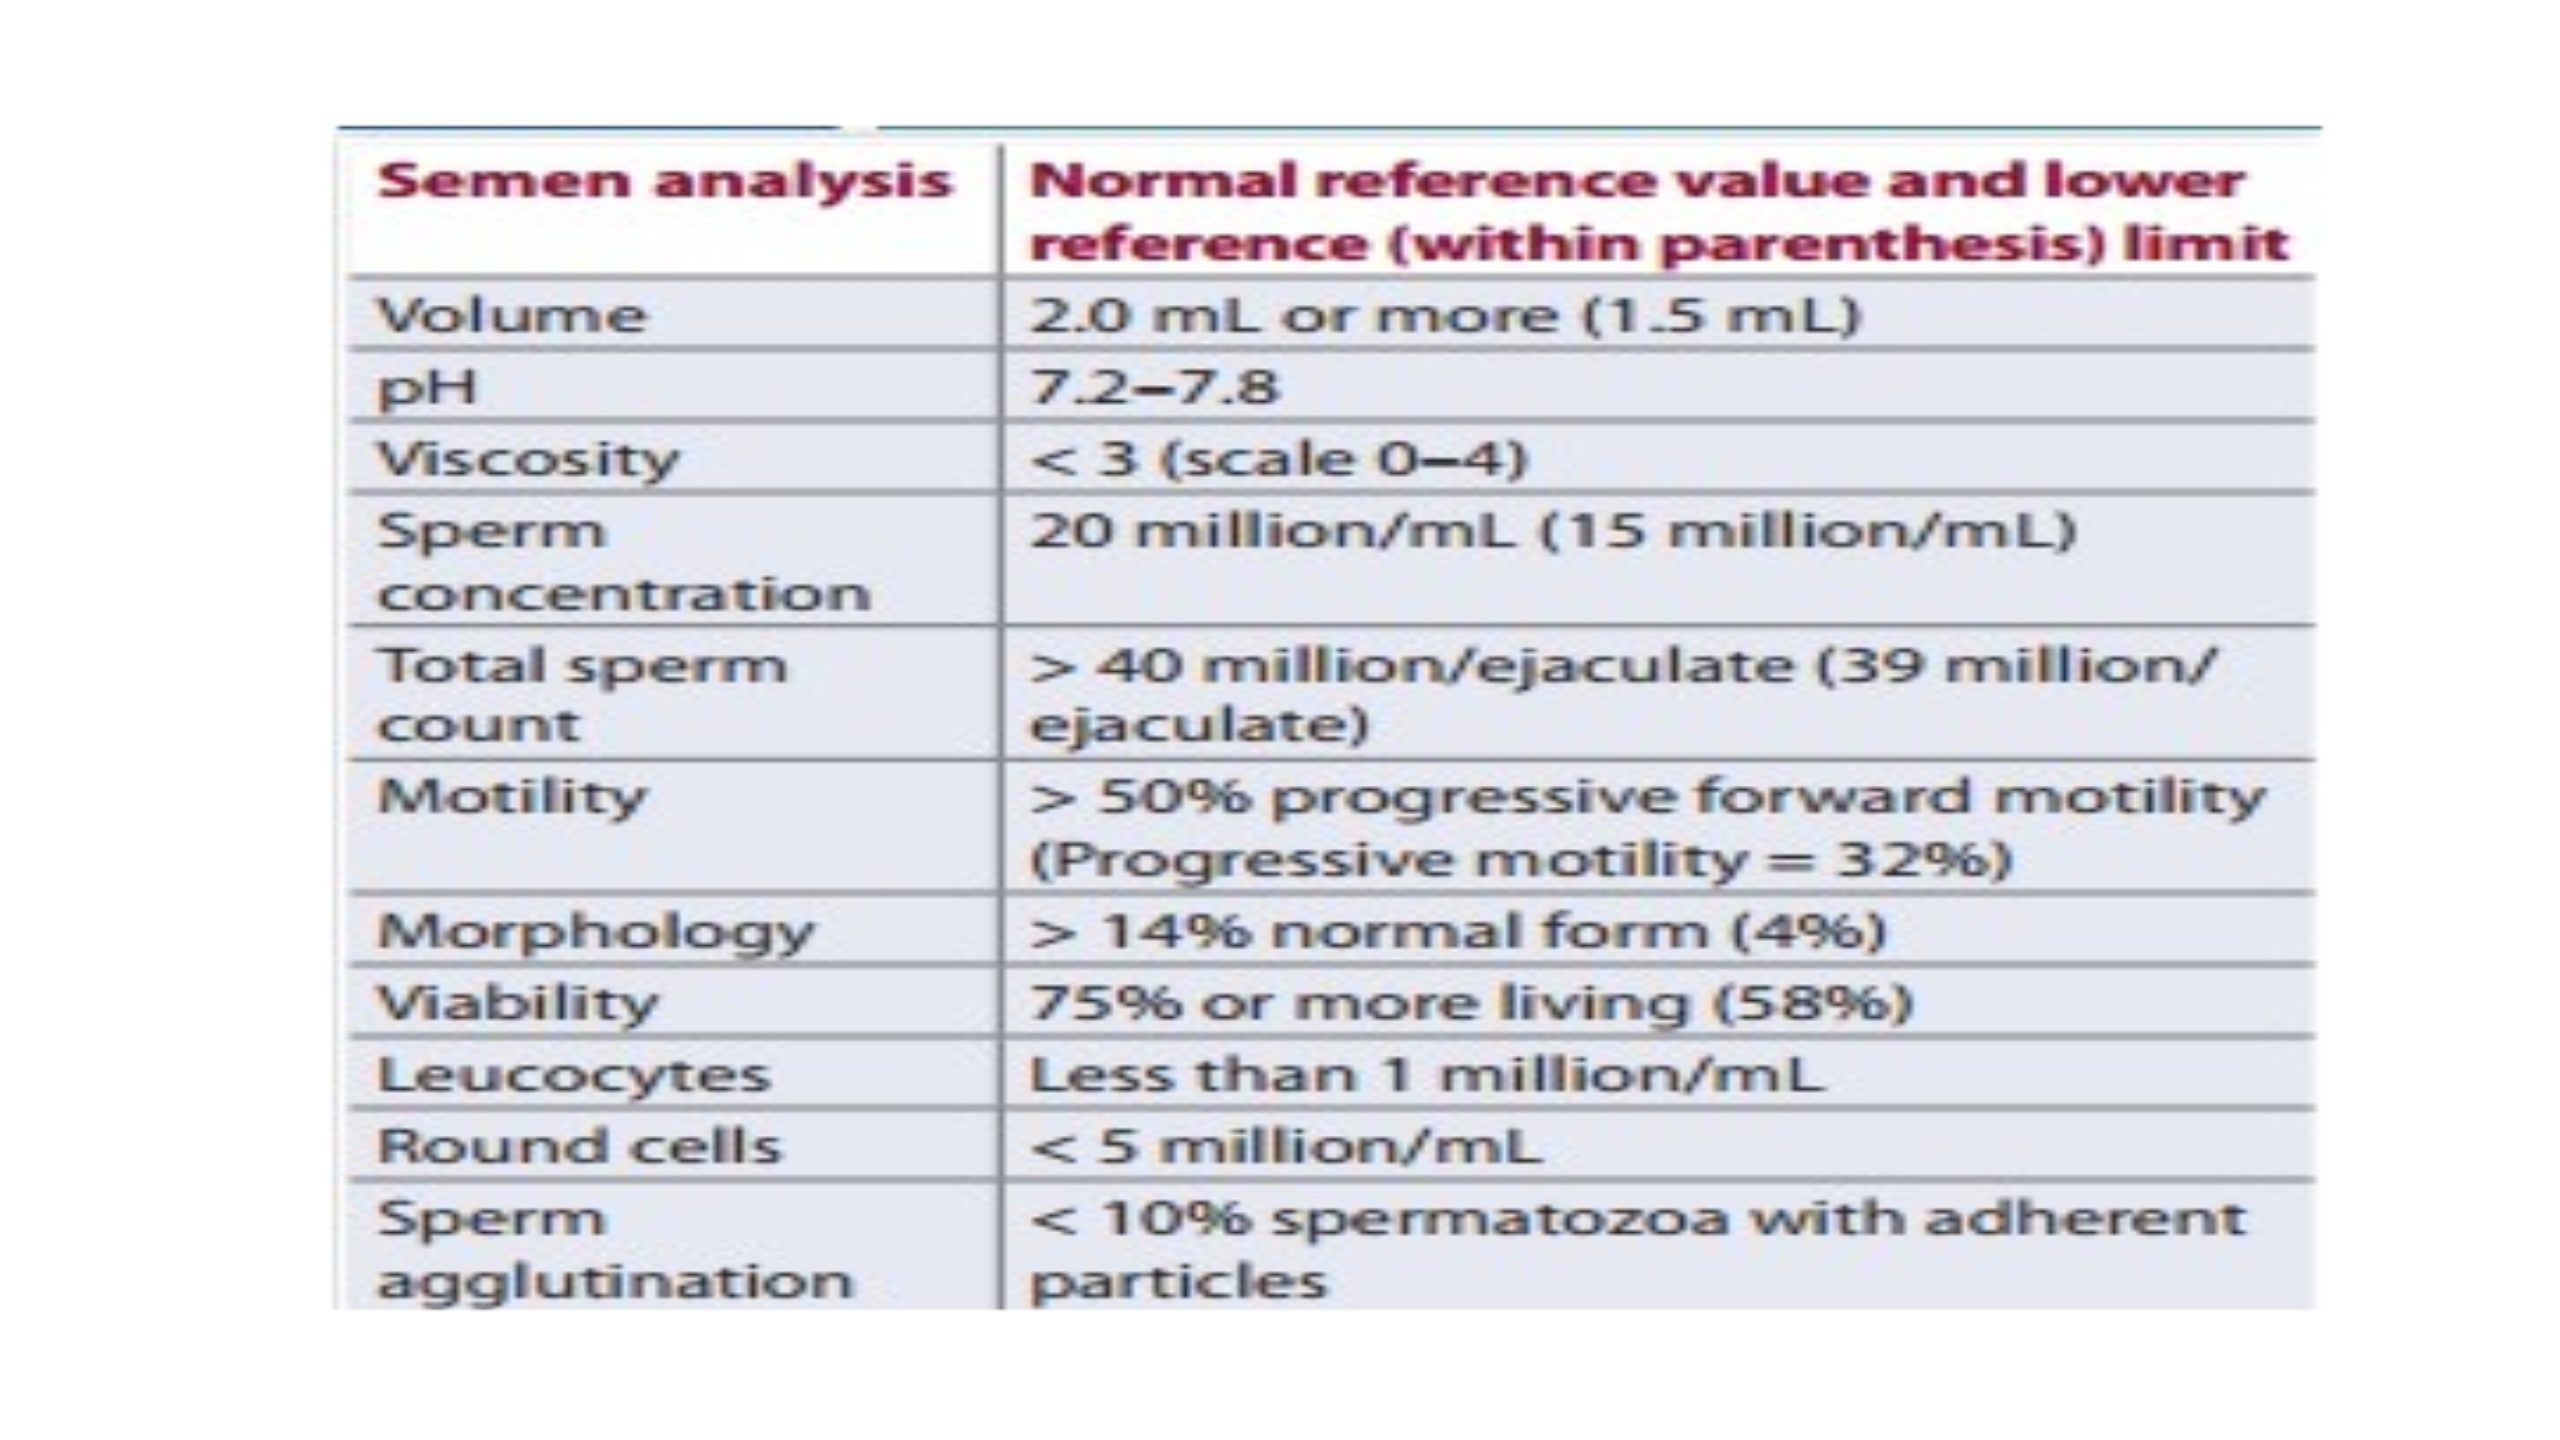
•Semen analysis: This should be the first step in investigation because,
if some gross abnormalities are detected (example being absence of
sperm), the couple should be counseled for the need of assisted
reproductive technology.
Normal
reference
value
and
lower
Worl
ur
2/0
molar
meore
(15
mL)
oH
7.2-7.8
Wiscosity
< 3
(scale
O—4)
Sern
#0
millian/smL
(15
mnillioms/mL)
concen
trait
kom
Total
sperm
>
40
million/ejaculate
(39
million’
Oc
Lrt
ejaculate)
Lortility
>
SOS
progressive
forward
motility
(Progressive
motility
=
32%)
Mor
phology
=
144936
meormal
forn$
(495)
Wiability
759)
OF
more
living
Son)
Leucocytes
Less
than
1
million/mLe
Round
cells
< 5
million/rmmbL
Sern
=<
10%
spenmatozoa
with
adherent
agglutination
partiches
TABLE
16.4
DIAGNOSIS
OF
OVULATION
Indirect
*
Menstrual
history
*
Evaluation
of
peripheral
or
endorgan
changes
-
BET
-
Cervical
mucus
study
-
Vaginal
cytology
-
Hormone
estimation
(see
Table
16.6)
—-
Serum
progesterone
—
Serum
LH
—
Serum
estradiol
—
Urine
LH
-
Endometrial
biopsy
*
Sonography
(TVS)
Direct
Laparoscopy
Conclusive
Pregnancy

•The anatomical patency and functional integrity of the tubes are
assessed by the following tests:
Dilatation and insufflation test (DI)
Hysterosalpingography (HSG)
Laparoscopy and chromopertubation
Sonohysterosalpingography
Falloposcopy
Salpingoscopy.

ASSISTED REPRODUCTIVE
TECHNOLOGY:
•The ART encompasses all the procedures that involve manipulation of
gametes and embryos outside the body for the treatment of
infertility.
• IVF is a type of assisted reproductive technology (ART) that involves
fertilizing an egg with sperm outside of the body and then
transferring the resulting embryo back into the uterus. The process
can be complex and involves several steps, such as ovarian
stimulation, egg retrieval, fertilization, and embryo transfer.

•PATIENT SELECTION (ideal)
Age < 35 years
Presence of ovarian reserve (serum FSH <10 IU/L).
Husband—normal seminogram.
Couple must be screened negative for HIV and hepatitis.
Normal uterine cavity as evaluated by hysteroscopy
/sonohysterography.

INDICATIONS OF IVF
Tubal disease
Unexplained infertility
Endometriosis
Male factor infertility
Multiple factors (female and male)
Failed ovulation induction
Ovarian failure (Donor oocyte IVF)
Women with normal ovaries but no functional uterus (Müllerian agenesis)
Women with genetic risk.

Principal steps of an ART cycle
1. Down regulation using GnRH agonist.
• GnRH agonist therapy used for down regulation of pituitary to prevent premature LH surge.
• GnRH agonist therapy is continued either subcutaneously or intranasally during the
gonadotropin treatment phase.
•Different schedules for GnRH agonist are
1. Long follicular down regulation
2. Long luteal down regulation
3. Short ‘flare’ protocol
2. Controlled ovarian hyperstimulation (COH).
Gonadotropin stimulation is begun once pituitary down regulation is achieved (serum E2 < 40
pg/ml and no ovarian follicles are seen > 10 mm on TVS

3. Monitoring of follicular growth.
•The follicular growth response is monitored by cervical mucus study,
sonographic measurement of the follicles and serum estradiol
estimation, commencing on the 8th day of treatment cycle.
•The endometrial thickness (stripe) ≥ 8–9 mm (trilaminar) is optimum.
•When two or more follicles are 17–18 mm in diameter and serum E2
levels > 250 pg/ml/per follicle, 5,000–10,000 IU of hCG (250).mg of
recombinant hCG) is given intramuscularly.
•Oocyte is retrieved 36 hours after the hCG is given. hCG induces
oocyte maturation.

4. Oocyte retrieval.
•Oocyte retrieval is done aseptically through vaginal route under
ultrasound guidance.
• With the development of vaginal transducers, vaginal needle aspiration is
done about 36 hours after hCG administration but before ovulation occurs.
5. Fertilization in vitro (IVF, ICSI, GIFT).
•The sperm used for insemination in vitro is prepared by the wash and
swim-up or density gradient centrifugation (preferred) technique.
•Approximately 50,000 to 100,000 capacitated sperm are placed into the
culture media containing the oocyte within 4–6 hours of retrieval.
•Sperm density and motility are the two most important criteria for
successful IVF. The semen is collected just prior to ovum retrieval.

6. Transfer of gametes or embryos.
•The fertilized ova at the 6–8 blastomere stage are placed into the
uterine cavity close to the fundus about 3 days after fertilization
through a fine flexible soft catheter transcervically. Not more than
three embryos are transferred per cycle to minimize multiple
pregnancy.The process of transfer should be accurate, atraumatic and
aseptic.

7. Luteal support with progesterone.
•It is started on the day after oocyte retrieval. hCG is given in supplemental
doses (1,500–2,500 IU). Micronized progesterone 200 mg thrice a day oral
or as vaginal suppository (preferred) or progesterone in oil injection 50mg
IM daily is continued for about 14 days. By this time diagnosis of pregnancy
by estimation of b-hCG (quantitative value) is possible.
•Result: The overall live birth rate varies from 32.7 percent per oocyte
retrieval..
•There is increased risk of miscarriage (18%), multiple pregnancy (31%),
ectopic (0.9%), low birth weight baby and prematurity. The risk of
congenital malformation of the baby remains similar to general population.

•PROGNOSTIC FACTORS FOR IVF-ET
1. Maternal age—there is age related decline in response to ovarian
stimulation, less oocytes, poor oocyte quality, less embryos and
implantation rate.
2. Ovarian reserve—declines with age.
3. Indication of IVF and past reproductive success. Women with tubal or
ovulatory factors, endometriosis, or unexplained factor—have higher
success rate compared to women with poor ovarian reserve.
4. Presence of hydrosalpinges—affect the outcome adversely.
5. Fibroid uterus—especially the submucous or interstitial variety have
adverse outcome.
6. Smoking—poor outcome.

