



1
DSM-5-TR- Jane
DSM-5-TR: Case Study Jane
Brittany Richardson
Liberty University: School Counseling Program
CEFS-546_D04 – Psychopathology
Dr. James Zapf
December 3, 2022
2
DSM-5-TR- Jane
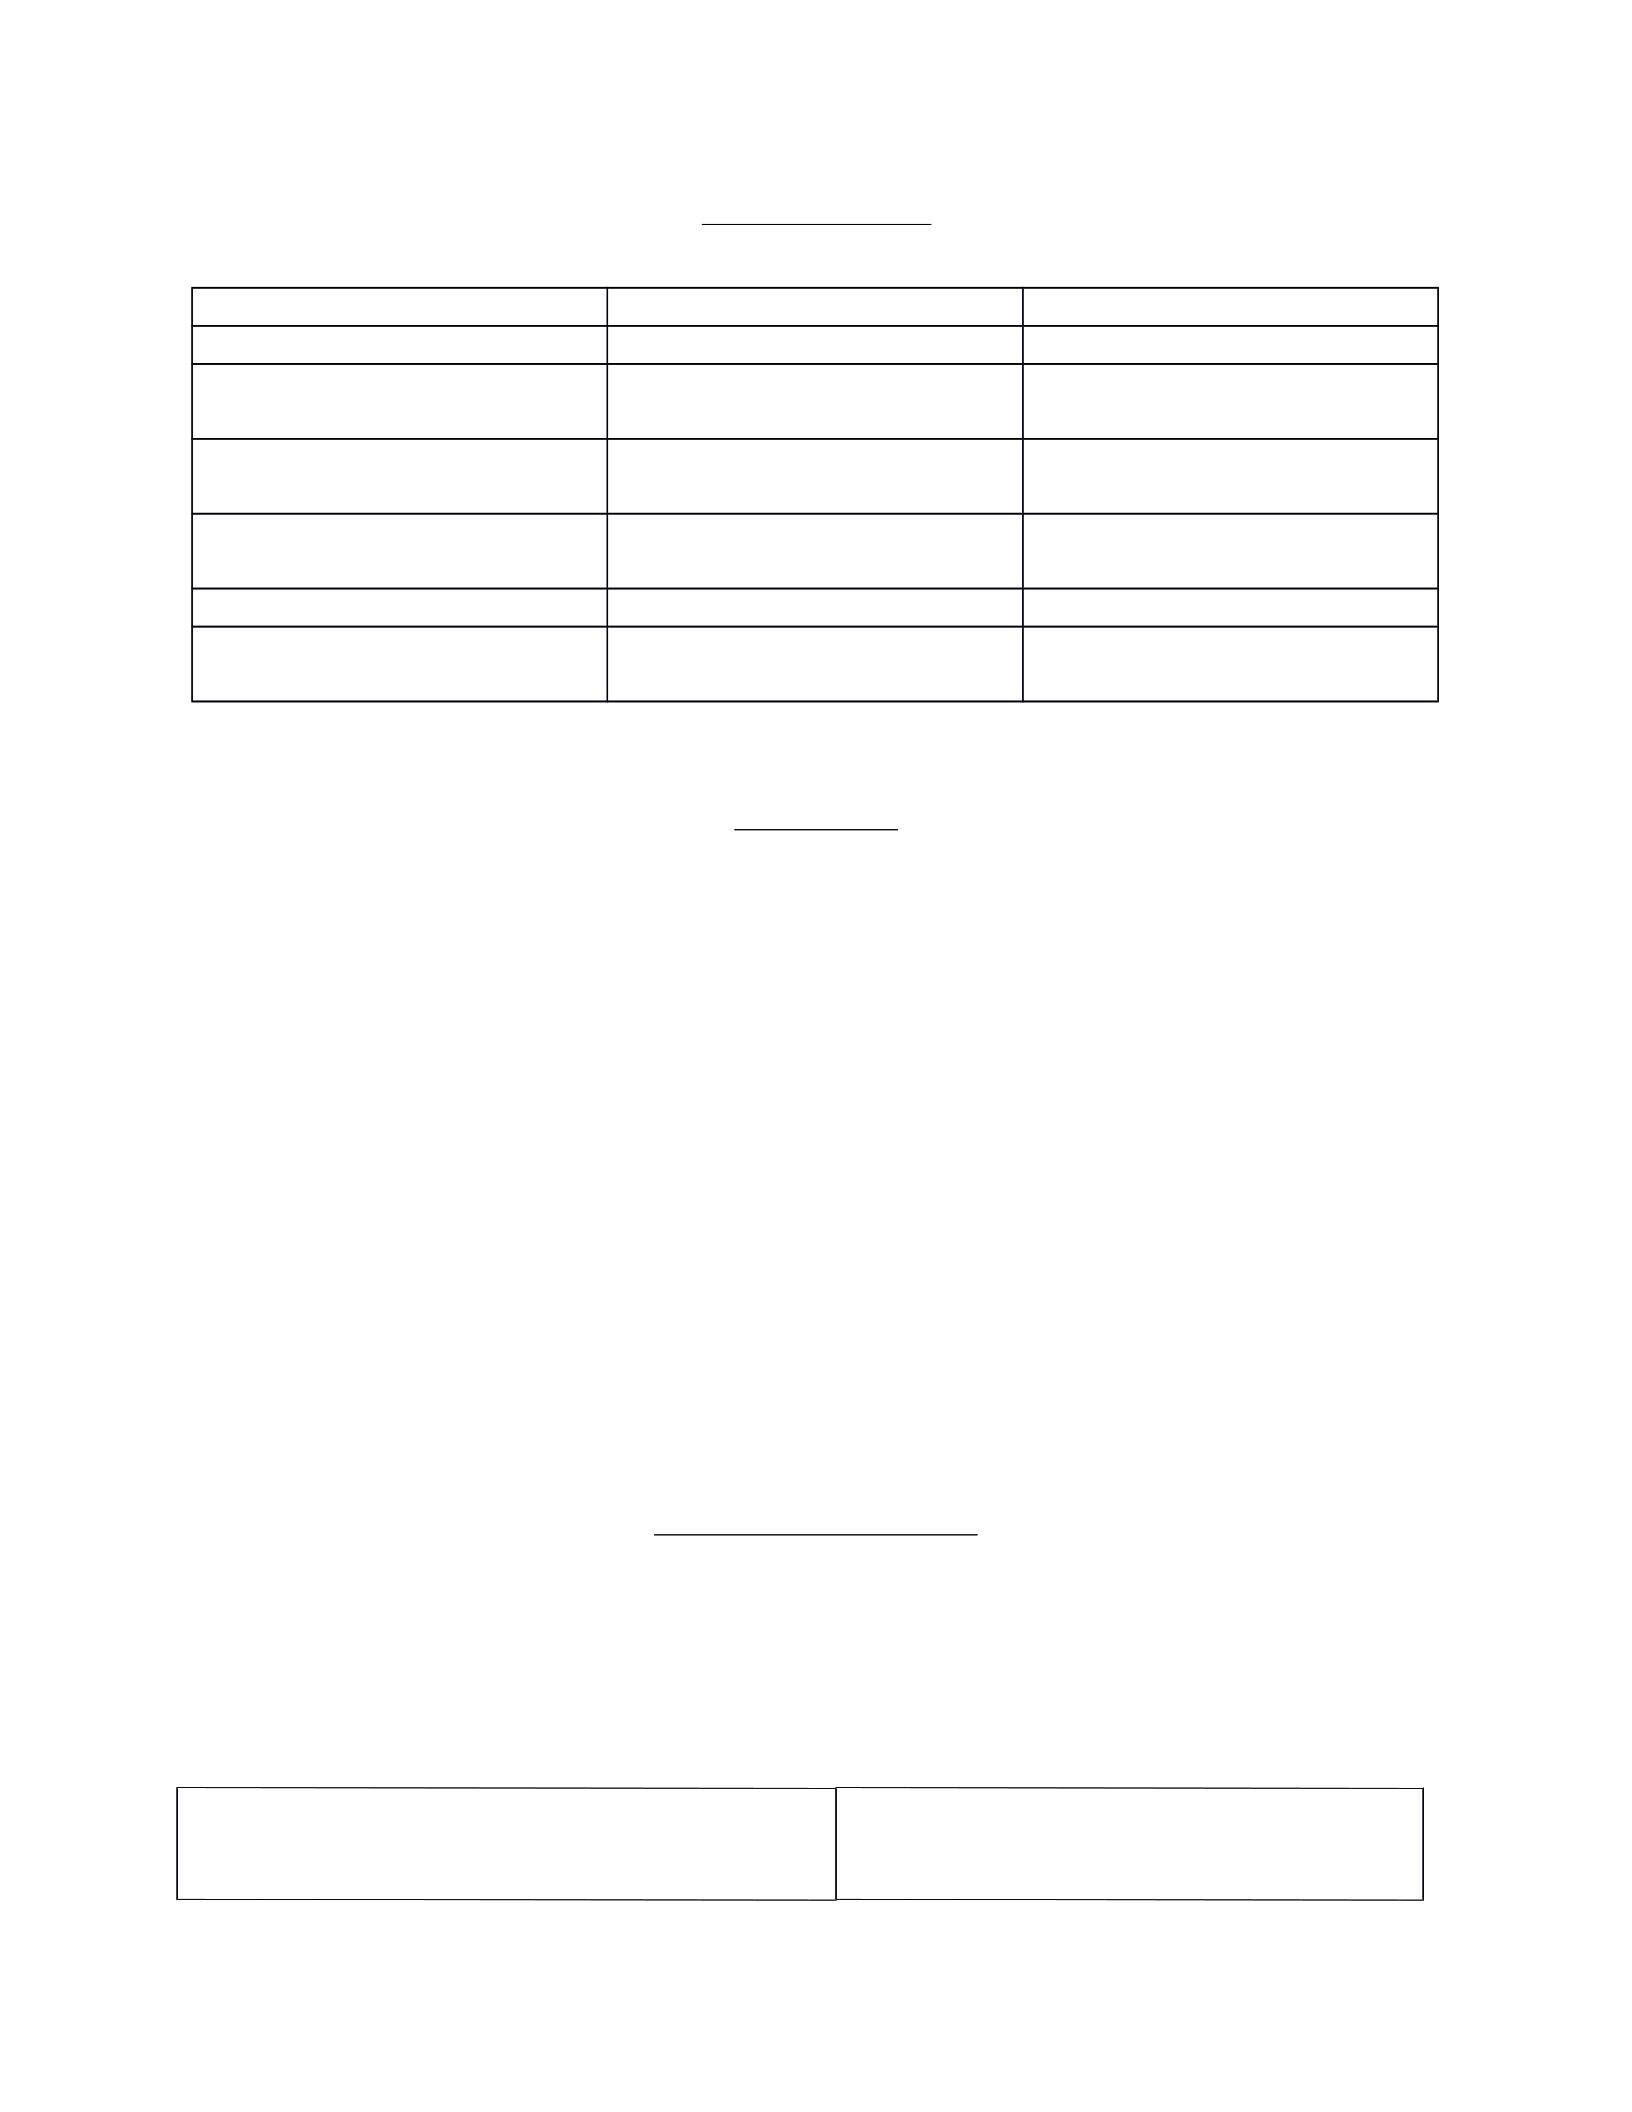
Client Concerns
Symptoms BehaviorsStressors
Anxious NightmaresCar accident
Sleeping problems Snapping at peopleWorrying about people being
upset with her
Difficulty sleeping Work performance going Not being able to go to
down church
Heart racing Not driving Feeling shameful for
questioning God
Irritability No social life
Flashbacks Losing sense of where she
was
Assessment
For Janes assessment I would chose ASDS Inventory. Bryant & Guthrie (2000) state,
“The Acute Stress Disorder Scale (ASDS) is a self-report inventory that (a) indexes acute stress
disorder (ASD) and (b) predicts posttraumatic stress disorder (PTSD). The ASDS is a 19-item
inventory that is based on Diagnostic and Statistical Manual of Mental Disorders”. This would be
good for Jane to be able to complete a self-inventory that she could reflect on. After completing
the assessment I would discuss the findings with her for any clarifications. Jane has so much
stress about the accident that I feel this would be more beneficial than asking her to recall the
whole accident again.
Diagnostic Impressions
Acute Stress Disorder- (F43.0)
Signs and Symptoms
DSM-5-TR Diagnostic Criteria: Acute Stress Client’s Signs/Reported Symptoms:
Disorder (F43.0)
3
DSM-5-TR- Jane
Criterion A: Exposure to actual or threatened Jane was in a car wreck where she was
death, serious injury, or sexual violence in one entrapped for 45 minutes and heard
(or more) of the following ways:screams from others. She was minimally
Directly experiencing the traumatic event(s).physically hurt but witnessed a lifeless
Witnessing, in person, the event(s) as it occurredperson be removed from another vehicle.
to others.
Learning that the event(s) occurred to a close
family member or close friend. Note: In cases of
actual or threatened death of a family member or
friend, the event(s) must have been violent or
accidental.
Experiencing repeated or extreme exposure to
aversive details of the traumatic event(s) (e.g.,
first responders collecting human remains,
police officers repeatedly exposed to details of
child abuse).
Note: This does not apply to exposure through
electronic media, television, movies, or pictures,
unless this exposure is work related.
Criterion B: Presence of nine (or more) of the Jane is having intrusive and recurring
following symptoms from any of the five thoughts about the car accident. She is
categories of intrusion, negative mood, having nightmares, and flashbacks. She is
dissociation, avoidance, and arousal, beginning having moments of dissociation, negative
or worsening after the traumatic event(s) mood and problems with sleep. She is
occurred:having difficulty concentrating. Jane has
Intrusion Symptomsremoved herself from social interactions.
Recurrent, involuntary, and intrusive distressing
memories of the traumatic event(s). Note: In
children, repetitive play may occur in which
themes or aspects of the traumatic event(s) are
expressed.
Recurrent distressing dreams in which the
content and/or affect of the dream are related to
the event(s). Note: In children, there may be
frightening dreams without recognizable
content.
Dissociative reactions (e.g., flashbacks) in which
the individual feels or acts as if the traumatic
event(s) were recurring. (Such reactions may
occur on a continuum, with the most extreme
expression being a complete loss of awareness
of present surroundings.) Note: In children,
trauma-specific reenactment may occur in play.
Intense or prolonged psychological distress or
marked physiological reactions in response to
4
DSM-5-TR- Jane
internal or external cues that symbolize or
resemble an aspect of the traumatic event(s).
Negative Mood
Persistent inability to experience positive
emotions (e.g., inability to experience
happiness, satisfaction, or loving feelings).
Dissociative Symptoms
An altered sense of the reality of one’s
surroundings or oneself (e.g., seeing oneself
from another’s perspective, being in a daze, time
slowing).
Inability to remember an important aspect of the
traumatic event(s) (typically due to dissociative
amnesia and not to other factors such as head
injury, alcohol, or drugs).
Avoidance Symptoms
Efforts to avoid distressing memories, thoughts,
or feelings about or closely associated with the
traumatic event(s).
Efforts to avoid external reminders (people,
places, conversations, activities, objects,
situations) that arouse distressing memories,
thoughts, or feelings about or closely associated
with the traumatic event(s).
Arousal Symptoms
Sleep disturbance (e.g., difficulty falling or
staying asleep, restless sleep).
Irritable behavior and angry outbursts (with little
or no provocation), typically expressed as verbal
or physical aggression toward people or objects.
Hypervigilance.
Problems with concentration.
Exaggerated startle response.
Criterion C: Duration of the disturbance
(symptoms in Criterion B) is 3 days to 1 month
after trauma exposure.
Note: Symptoms typically begin immediately
after the trauma, but persistence for at least 3
days and up to a month is needed to meet
disorder criteria.
Criterion D: The disturbance causes clinically
significant distress or impairment in social,
occupational, or other important areas of
Jane has felt this way for 15 days- ever
since the wreck.
Jane has changed almost everything in her
life to keep her from possibly experiencing
something traumatic again. She is not
5
DSM-5-TR- Jane
functioning.driving, seeing her children or parents and
not going to church.
Criterion E: The disturbance is not attributable toJane does not use alcohol or substances
the physiological effects of a substance (e.g., and does not have any other medical
medication or alcohol) or another medical conditions.
condition (e.g., mild traumatic brain injury) and
is not better explained by brief psychotic
disorder.
Other DSM-5-TR Conditions Considered
Post-Traumatic Stress Disorder (F43.10). I considered PTSD, but Jane does not meet all
criterion. She meets criterion A-D, G & H, but not E. Her symptoms have only been present for
18 days and PTSD requires longer than a month. She could develop PTSD, but it is too early to
tell.
Developmental Theories and/or Systemic Factors
Jane is in the generativity vs. stagnation stage of Erikson’s theory. In this stage the
individual tries to contribute to others around them or “give back” to something that will outlast
them. Jane displays this by taking care of the church, working, her parents and visiting with her
children. Since her wreck Jane seems to be stagnant and without treatment to help cope I am
afraid she will be stuck in stagnation. Jane has been married for 54 years and seems to have had a
pretty consistent lifestyle prior to the accident. This accident and the stress that came along with
it was completely unexpected for Jane.
Multicultural and/or Social Justice Considerations
Jane is a 54-year old, black female. She has been married for 33 years and has 2
children- one is 25 and the other is 31. She attends church and is active in her church community.
Jane works for a large company where she is very successful, but the toll that the wreck has

6
DSM-5-TR- Jane
taken on her is starting to interfere with her job. Jane being a black female is a minority in itself.
Jane has probably worked very hard for her position in her company, especially with her age and
consideration of her gender and race, combined. This makes it even more stressful for Jane to
think she could possibly lose her job, or her position that she has worked so hard for. Acute
Stress Disorder is more prevalent in women vs. men, and her race makes her more at risk.
Treatment Recommendations
Key Issues for Treatment
Flashbacks
Difficulty Sleeping
Anxiety
Recommendations for Individual Counseling
I would chose trauma focused cognitive behavioral therapy for Jane. Fanai (2022) states,
“treatment of choice for acute stress disorder (ASD) is a unique form of cognitive-behavioral
therapy (CBT) called trauma-focused CBT. CBT can reduce the risk of further developing
PTSD”. Jane is not excited about attending individual therapy, but says she’s willing to do it. I
would talk more with Jane about her spiritual beliefs and try to incorporate into her therapy
sessions, however she feels comfortable. I would not start with incorporating any medication
treatment based on past studies. If Jane’s sleep did not improve after starting therapy I would
maybe recommend medication to help her sleep.
Specific Considerations
A triggering event could cause immediate intervention if it caused psychotic features,
hallucinations or severe disassociation. In our initial treatment planning I would talk with Jane

7
DSM-5-TR- Jane
about different scenarios and let her know that certain circumstances will need immediate
attention. I will stress the importance to her, and ask her to share with her husband as well in case
she gets in a crisis mode. A barrier for Jane is that if she needs to see me immediately and her
husband is not home, she will not be in a position to drive herself to a visit. We could make it
work with a phone call in this case. Another barrier could be trying to create a treatment plan
with Jane right now when she is a state of anxiety and having mild disassociation randomly. It
would be beneficial to have Jane’s husband present if she gave consent.

8
DSM-5-TR- Jane
References
Bryant, R. A., Moulds, M. L., & Guthrie, R. M. (2000). Acute Stress Disorder Scale: a self-report
measure of acute stress disorder. Psychological assessment, 12(1), 61–68.
Fanai M, Khan MAB. Acute Stress Disorder. [Updated 2022 Jul 12]. In: StatPearls [Internet].
Treasure Island (FL): StatPearls Publishing; 2022 Jan-. Available from:
https://www.ncbi.nlm.nih.gov/books/NBK560815/
Psychiatry online. DSM Library. (n.d.). Retrieved November 6, 2022, from
https://dsm.psychiatryonline.org/

