


1
Section 1: Introduction and Background
Overall Goals of the Dissertation
Twenty years after the introduction of luxury accommodations, hotel room cleaners continue to
face the uncontrolled ergonomic hazards associated with hotel room cleaning. Upon the
promulgation of Cal/OSHA 3345 in 2018 – an occupational health regulation for the prevention
of musculoskeletal injuries occurring to hotel housekeepers, then Cal/OSHA Chief Sum stated,
“Hotel housekeepers have higher rates of acute and cumulative injuries compared to workers in
other industries, and data shows those injuries have steadily increased…”. This regulation
requires employers to identify, evaluate and correct housekeeping-related hazards….”.1,2 Hotel
room cleaner reports of increased workload and consequential pain are supported by worker
surveys and biomechanical studies demonstrating a high risk of low back disorders by specific
hotel room cleaning job tasks.3-9 Research is needed to characterize musculoskeletal disorder
injuries (MSDs) occurring to hotel room cleaners and to identify tasks associated with MSDs.
This includes injuries occurring to parts of the body other than the lower back such as shoulders,
elbows, knees, etc.10 Researchers call for expanded analyses of hotel room cleaner injury risk
factors and application of ergonomic interventions to decrease exposure to MSD risks when
performing hotel room cleaning tasks 11,12
The goals of this dissertation are to identify hotel room cleaners as an occupation experiencing
work-related musculoskeletal injuries (Aim 1), identify task at time of injury (Aim 2), provide a
descriptive analysis of hotel room cleaner MSD injuries (Aim 3A) and explore the relationship

2
between task and injury outcomes (Aim 3B) using narrative text data from workers’
compensation claims. These goals attempt to address the data gaps described below. In carrying
out the aims of this dissertation, the occupation of hotel room cleaner and the task at time of
injury were identified and coded, making data analysis possible. Data analysis then described
worker and injury characteristics and associations between task and injury outcomes. The
findings from my dissertation analyses contribute new information to aid in targeting injury
reduction efforts by nature of injury (e.g., sprain or strain), cause of injury (e.g., lifting or
pushing or pulling), and part of body injured. Moreover, these findings lay the foundation for
hotel room cleaning task-specific worksite interventions. The ideal administrative data that
combines demographic, employment and occupation and injury information is workers’
compensation data. The source data for my dissertation is California workers’ compensation
claims data for hotel industry employees.
Significance of Data Gaps Addressed by Dissertation Goals
Although the Bureau of Labor Statistics (BLS) publishes injury rates and injury and worker
characteristics by industry, e.g., hotels, and by occupation, e.g., maids and housekeepers, the
BLS does not publish cross-referenced BLS occupation injury rate data with BLS industry data.
Therefore, what we know about hotel room cleaner work-related pain and injury comes mostly
from academic studies. Lacking from the literature are peer-reviewed studies using
administrative data such as workers’ compensation data.
The lack of occupational injury surveillance data and peer-reviewed administrative data studies
about hotel room cleaner MSDs is significant for several reasons and at the key intervention
levels of industry, occupation and worksite (hotel). First, at the industry level, the U.S. traveler
3
accommodation industry (NAICS 7211) ranks number one among all industries (Table 1.1) for
employing Maids and Housekeeping Cleaners, representing 59.8% of the total employment by
the top five industries for this occupation.13 Maids and Housekeeping Cleaners is the Census
Bureau’s standard occupation classification “SOC 37-2012” with job tasks most similar to those
of hotel room cleaners.14 In 2018, the hotel industry’s incidence rate for nonfatal occupational
injuries and illnesses was 1.5 times the rate for private industry, indicating an excess of injuries.15
Second, at the occupation level, Maids and Housekeeping Cleaners are a high-risk occupation for
MSDs, ranking among the BLS’s ten high-risk occupations for MSDs for all industries for 2017
with an incidence rate more than three times that for all workers with
MSDs.16 Third, at the worksite (hotel) level, the occupation of Maids and Housekeeping Cleaners
accounts for 23% of the workforce in the traveler accommodation industry, the largest proportion
overall, making this occupation a hotel’s largest workforce.13
For a high-risk worker population employed in an industry with high rates of nonfatal
occupational injuries and illnesses that is the leading employer for this workforce, the lack of
surveillance data is a serious obstacle to employer and public health injury prevention and
control efforts.
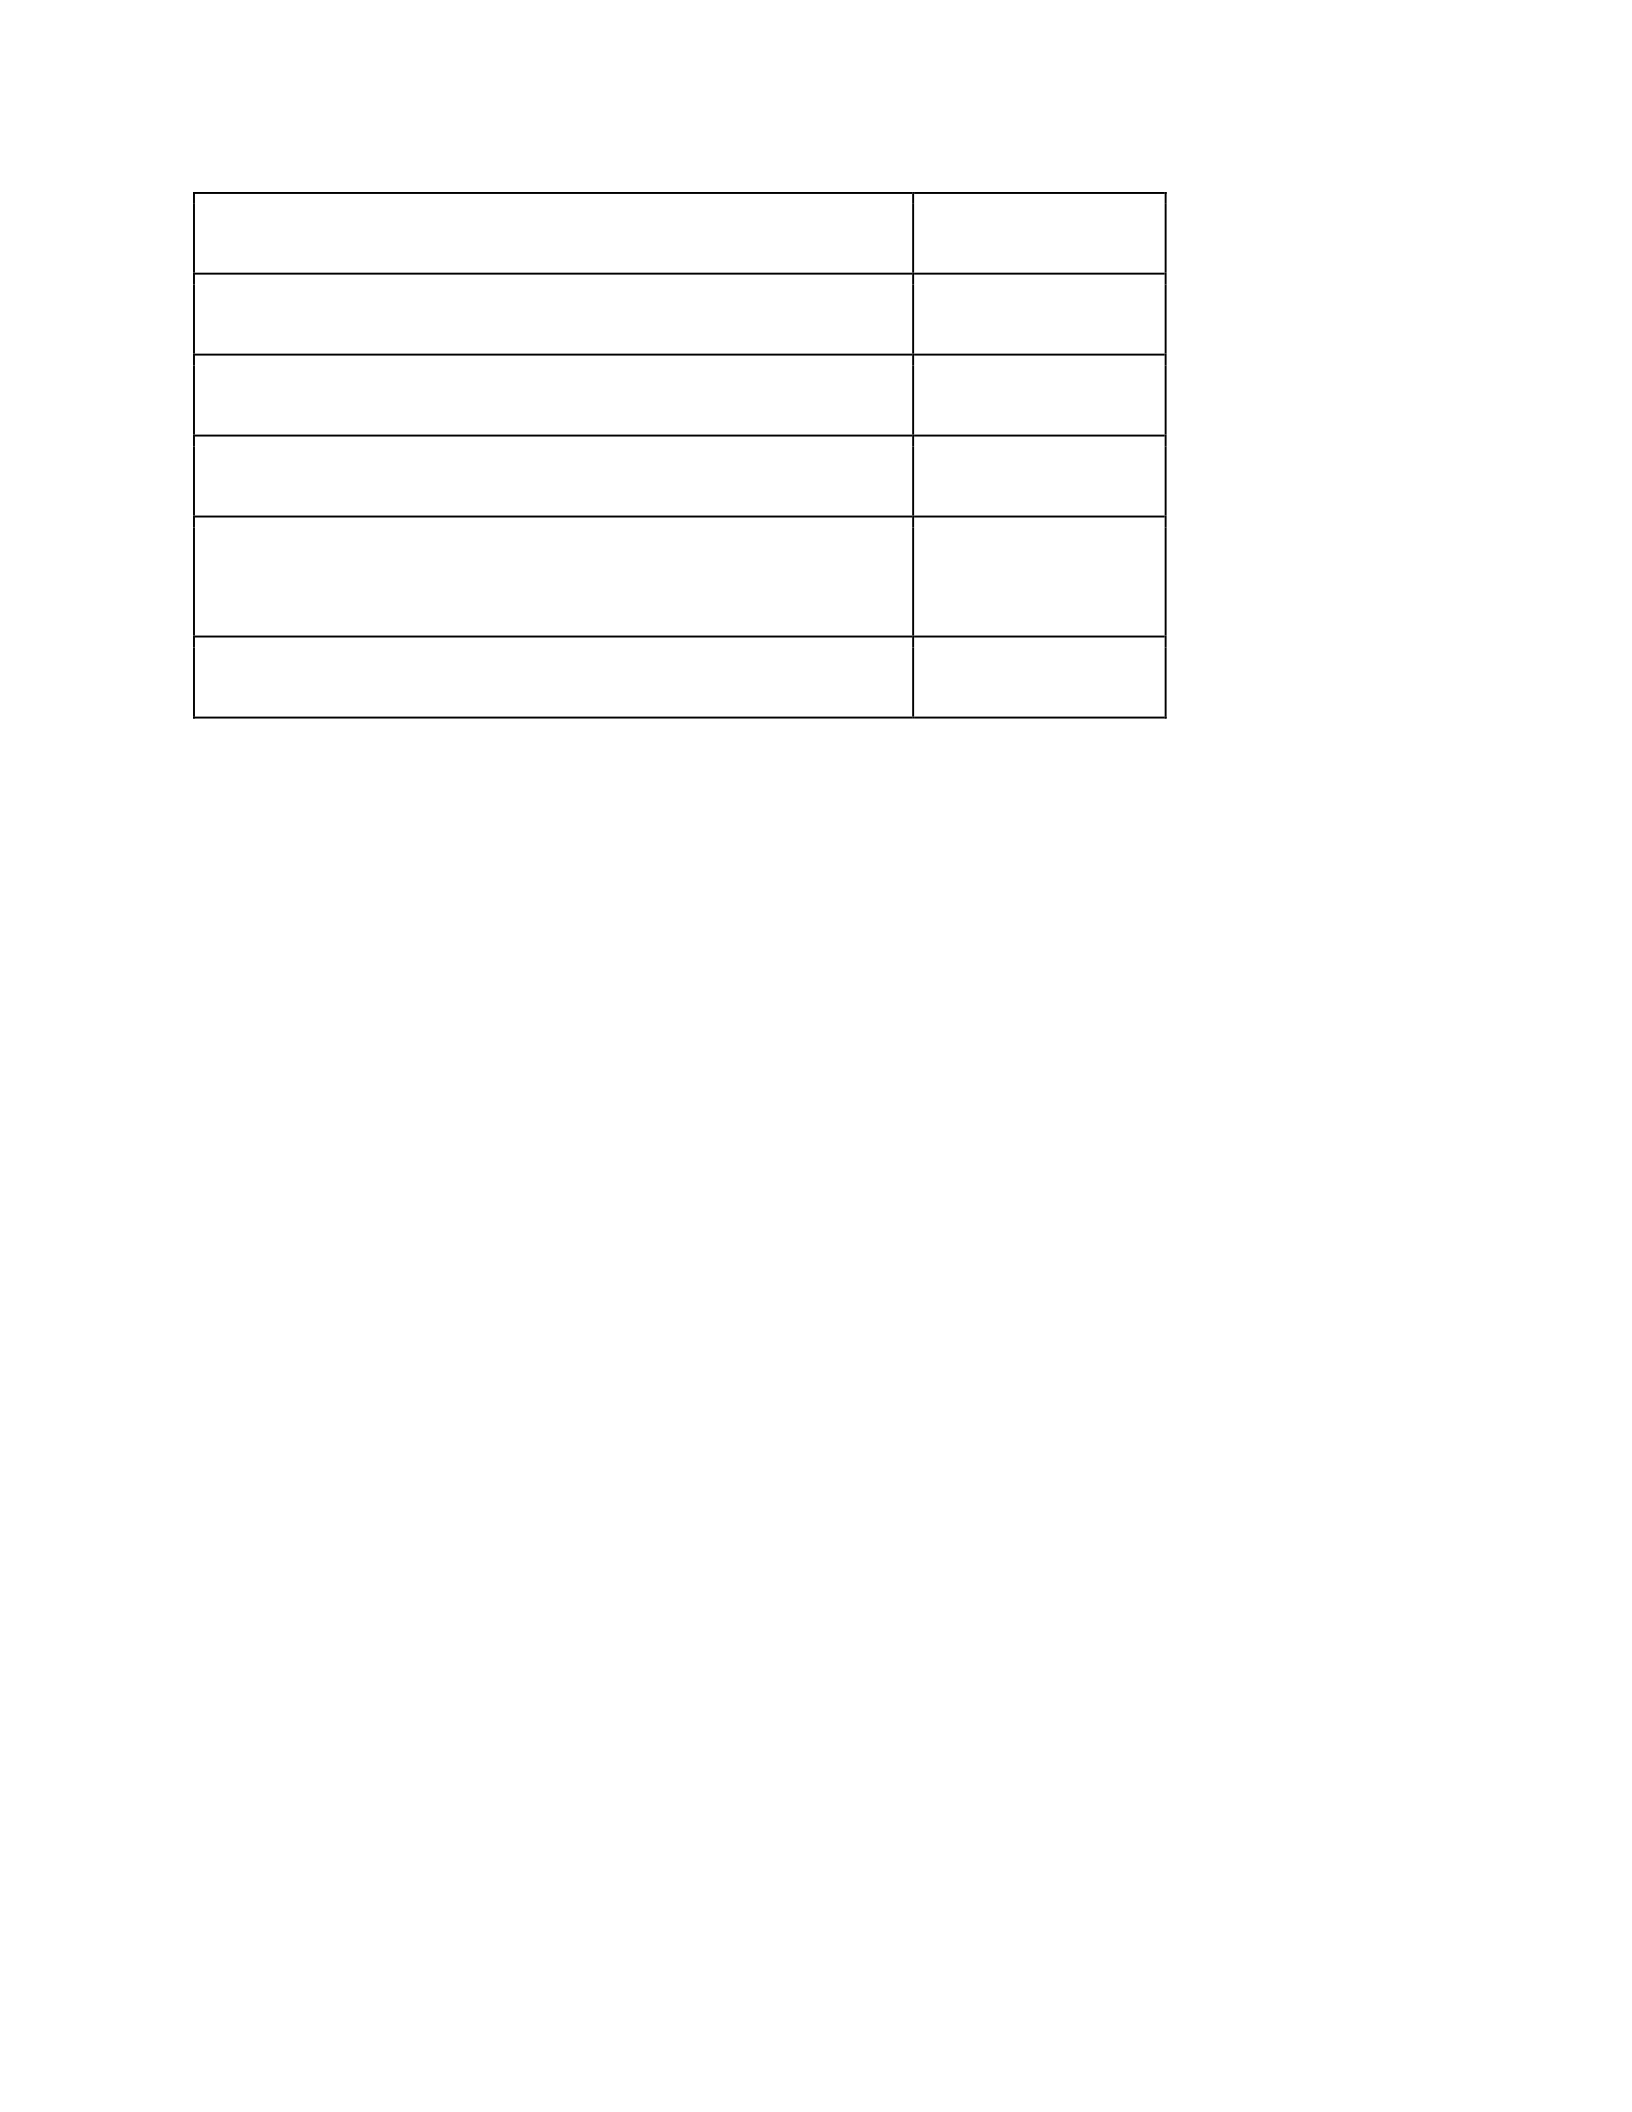
Table 1.1 Five Industries with the Highest Levels of Employment for Maids and
Housekeeping Cleaners. Occupational Employment and Wages, May 2019. Bureau of Labor
Statistics
Industries Employing 37-2012 Maids and Housekeeping Cleaners
Industry
Employment
4
Travel Accommodation
467,270
Services to Buildings and Dwellings
100,490
General Medical and Surgical Hospitals
95,050
Nursing Care Facilities (Skilled Nursing Facilities)
71,480
Continuing Care Retirement Communities and
Assisted Living Facilities for the Elderly
46,480
Total employment, top five industries
780,770
Part 1. Public Health Issue of Concern: Musculoskeletal Disorder Injuries and Hotel Room
Cleaners
a. What do we know about the hotel room cleaner workforce?
Who are hotel room cleaners?
In the United States, hotel room cleaners are a predominantly female workforce with a large
percentage of Hispanics/Latinas followed by Asian/Pacific Islanders and African-Americans.7,10
Using data from the U.S. Census Bureau’s standard occupation classification of 37-2012 Maids
and Housekeeping Cleaners, 85.3% of this workforce is female and the average age for female
hotel room cleaners is 44.7 years.17,18 Immigrants account for the majority of hotel room
cleaners.7 Studies identify musculoskeletal disorders due to awkward postures as a concern for
immigrant cleaners who face multiple barriers such as low literacy skills, few resources and
cultural factors.19 Latina and immigrant hotel room cleaners were reported to experience

5
occupational disparities including higher injury rates for hotel housekeepers who identified as
Hispanic compared to their white counterparts.10,20
There are a variety of occupational terms used for this workforce, e.g., hotel maid, hotel
housekeeper, guest room attendant or room attendant, all of which are occupations in a hotel’s
housekeeping department. An additional job classification, housemen/housepersons is often
discussed along with hotel room cleaners as it is the job classification in a hotel’s housekeeping
department that removes dirty linens from guest rooms and cleans extra dirty rooms.
Historically, housemen had been a predominantly male occupation; in recent years, this job
classification is referred to as “housepersons” as more women are filling these jobs. For the
purposes of my research, the all-encompassing term ‘hotel room cleaner’ will be used throughout
this dissertation except for where the text refers to other terms used in the scientific literature
and/or government sources.
What Job Tasks Does a Hotel Room Cleaner Perform?
Hotel room cleaning is physically demanding work. Tasks associated with hotel room cleaning
include: making beds, vacuuming guest rooms, dusting, cleaning tubs and shower walls,
scrubbing bathroom floors, cleaning mirrors, polishing furniture, removing trash, pushing carts
and moving furniture to perform room cleaning tasks, e.g., to vacuum, to clean under beds.21-23
Hotel room cleaners are required to clean a certain number of rooms during a shift, known as the
“daily room quota.” The daily room quota is broken down by the number, room status and type

6
of room the hotel room cleaner is assigned to clean. For example, there are two categories of
room status, each one with a corresponding level of housekeeping service: stay over (guest is
staying another night), and check outs (guest is checking out), with check outs requiring more
cleaning work as the guest room is prepared for a new guest. The type of room includes: king
(king-size bed), double doubles (a guest room with two double beds) and suites or VIP rooms
(may include a living room with a sofa bed and a kitchenette) with the latter two types requiring
more work and greater physical demand. Hotel room cleaners report working quickly, taking
shorter breaks or none at all and working long hours to meet these quotas.6
b. What do we know from existing research about work-related injuries of hotel room cleaners?
Work-related Injury Rates of Hotel Room Cleaners
A study of U.S. hotel workers was undertaken using employers’ records of 2,865 work-related
injuries during 55,327 worker-years of exposure and hiring data that provided job tenure and
self-identified gender and race/ethnicity information.10 The study authors, academics and hotel
union-based researchers, found that by occupation, room cleaners had the highest rate of
workrelated injuries overall, the highest rate of MSD injuries, and the second-highest rate of
acute trauma compared to all hotel workers studied. In addition, when comparing by
race/ethnicity among hotel room cleaners, Hispanic hotel room cleaners had an 82% greater
chance of an MSD injury than white female room cleaners studied. This is the only study
reporting work-related injury rates in the United States by hotel worker occupations.

7
Work-related Pain Prevalence Rates
Findings from housekeeper surveys performed by academic researchers and labor union staff,
describe high prevalence rates of work-related pain, yet low rates of reporting such pain to
employers, highlighting that underreporting of work-related injuries is prevalent among hotel
room cleaners.4-7 All of these studies took place after the increase in luxury accommodations
which occurred in the hotel industry in the late 1990s. These low rates of reporting work-related
pain to employers occur despite high rates of prevalence of severe bodily pain, of medication use
and of doctor visits.4-6 In a study by university faculty and a labor union, Lee and Krause found
that of 258 unionized hotel room cleaners surveyed from four San Francisco hotels, 77% had
work-related pain in the past year; 73% of cases reported going to a doctor and 53% stayed home
from work, yet only 50% reported the pain to management and even less, 23% filed a formal
injury report in the past year.5 In a study of 941 hotel room cleaners from union hotels in Las
Vegas about increased workload, Krause and co-authors found that 47% of those surveyed
reported severe pain in the past four weeks and 84% took medication for pain they experienced
in the workplace in the same time period.6 In the same study, 78% of hotel room cleaners
reported experiencing pain the past 12 months that they believed to be work-related; of these,
62% went to a doctor for the pain. Similar findings were described in a report by UNITE HERE,
the hospitality workers’ union representing workers in North America. From 600 hotel
housekeepers surveyed in the U.S. and Canada, 91% reported work-related pain. Of those
reporting pain, 66% took pain medication and two-thirds visited their doctor because of the
pain.4 In a study by Scherzer and co-authors using the responses from the same surveyed 941
unionized hotel room cleaners from five Las Vegas hotels, 31% reported pain to management and
20% reported a workers’ compensation injury, with 35% of claims denied.7

8
Causes of Work-Related Hotel Room Cleaner Pain and Injuries
There are several factors that contribute to the causes of occupational hotel room cleaner pain
and injuries. These include the physically demanding nature of the work, failure by the hotel
industry to control the hazards associated with hotel room cleaning, changes in hotel guest
accommodations that increase workload, green programs that reduce staffing and increase injury
risk, aspects of how the work is organized (room quota, speed-up), reduction in staffing in the
hotel’s housekeeping department and lack of recognition by the hotel industry of the impact of
these factors on hotel room cleaners’ health. These factors are described in detail below.
c. What do we know about hotel industry changes in guest accommodations?
Intensification of Competition in the Hotel Sector
Competition for hotel guests has resulted in changes over the past twenty years by the hotel
industry that include providing luxurious sleeping accommodations, promoting hotel ‘green
programs’ to guests and reducing housekeeping staff. These changes were introduced in hotel
guest rooms starting in 1999, a period known as the “Bed Wars” where each hotel company
“brands” (differentiates) its bed package (mattress, sheets, duvets, pillows) from those of other
hotel companies, e.g., the Westin’s Heavenly Bed, the Radisson’s Sleep Number Bed.24
Intensification of Hotel Room Cleaner Workload
Fancy bedding such as triple sheeting, thick duvets, high thread-count sheets and more pillows
are the standard today, increasing the number of pounds of linen per hotel guest room.25 Hotel
luxury accommodations include mattresses that weigh over 100 pounds and duvets that can
weigh 14 pounds.26,27 For hotel room cleaners, this means forceful lifts during bedmaking and

9
heavier linens to pull off when stripping the beds. While these changes in hotel accommodations
occurred, the hotel industry also adopted lean staffing models that reduced the number of hotel
room cleaners and housemen, two key job classifications in a hotel’s housekeeping department.28
As a result of staffing cuts, the tasks of housemen were added to those of hotel room cleaners.
For example, heavy loads of dirty linens previously removed by housemen, are now added to
housekeeping carts already laden with the usual load of clean linens, towels, amenities and
vacuum cleaners. These carts are pushed by hotel room cleaners from room to room down
carpeted hallways and in and out of elevators to clean rooms on different floors.26
Renovations are another way to keep hotels competitive with the most recent change being the
installation of floor to ceiling glass shower doors and walls. Hotel room cleaners complain of a
lack of additional time and long-handled tools to clean the glass doors and walls. Instead,
cleaning is performed by extended reaches of the hotel room cleaner’s arm(s) above the
shoulders, adding forceful exertions and strain. Testimony from hotel room cleaners in support of
a state-level regulation proposed by the California Department of Occupational Safety and
Health to prevent musculoskeletal injuries in hotel housekeeping raised the following concerns:3
“Candy Hu, Hotel Housekeeper, Unite Here Local 2, ... “the hardest part of her job is cleaning
the bathroom because she must stand on her tiptoes and reach up high to clean the top part of the
glass shower doors.”
“Irma Perez, Hotel Housekeeper, Unite Here Local 2850 Oakland, … “it is important that
employers provide hotel housekeepers with the proper tools to do their jobs safely, and that they
also provide training for their housekeepers and supervisors on how to use those tools properly.”

10
“Olga Manrique, Hotel Housekeeper, Unite Here Local 19, … “many housekeepers must reach
up high to clean walls and other surfaces, and as a result of not having the proper tools, they
injure their arms and backs.”
Increased workloads associated with changes in hotel accommodations and hotel renovations
described above, coupled with the room quota system, contribute to setting the pace at which
tasks get done; pace then determines whether a slower, safer room cleaning work practice is
performed versus a quicker, less safe one.
Another way of marketing a particular hotel company’s brand is by offering guests the hotel’s
‘green’ program. Hotel green programs were established ostensibly to reduce water, energy, and
detergent usage, with over 6 million Starwood Hotel guests taking part in such programs since
2009.29 These green programs depend on a hotel guest’s refusal of daily room cleanings in
exchange for receiving food and beverage coupons or loyalty points in a hotel’s guest rewards
program where you can apply points towards a hotel stay. When comparing employment and
injury data for 2013 and 2017, a study of 23 hotels in nine U.S. cities that practiced green
programs found a decrease of 700,000 total work hours (the equivalent of 350 full-time jobs) and
a 49% increase in injuries.30
d. What is the public health significance of musculoskeletal disorder injuries?
According to the Centers for Disease Control, “musculoskeletal disorders (MSD) are injuries or
disorders of the muscles, nerves, tendons, joints, cartilage, and spinal discs”.31 The World Health

11
Organization characterizes musculoskeletal injuries as those accompanied by pain and restriction
of movements, resulting in permanent work disability, income loss and limitations in social
interactions.32 The National Institute of Occupational Safety and Health (NIOSH) defines a
subset of musculoskeletal injuries to be “work-related musculoskeletal disorders (WMSDs)”
where “the work environment and performance of work contribute significantly to the condition
or where MSDs are made worse or longer lasting by work conditions”.33
Approximately one-third of all occupational injuries in the United States are musculoskeletal
injuries, which also account for the majority of lost or restricted work-time cases.34 WMSDs are
costly, result in lost productivity and substantial human suffering. For example, for the United
States in 2007, the average medical cost of an individual work-related MSD case was $2,924
dollars; the total estimated costs for WMSDs nationally was $3.4 billion, with adjustments for
underreporting.35 An additional $1.1 billion is estimated in costs for lost workdays of injured
workers and replacing employees permanently disabled for the same time period.35 Examples of
how WMSDs interfere with workers’ routine activities range from bathing to childcare and can
include financial disruption resulting in car and home loss.36 Ergonomic interventions are
recognized as the next step towards reducing worker MSD injuries and employer workers’
compensation costs.34 Since my focus is on work-related hotel room cleaner MSDs, these
injuries will be referred to simply as MSDs, not WMSDs, throughout this dissertation.
The Importance of Low Back Disorders
Research about musculoskeletal disorder injuries occurring to hotel workers from four job titles –
hotel housekeeper, kitchen worker/cook, dishwasher/steward and banquet server - identified the

12
back as the most common (40%) part of body injured, with other research finding the lower back
reported as the most frequent (63%) site for severe pain.6,10 Low back disorders are the most
frequent type of work-related musculoskeletal injury and can negatively impact a worker’s
quality of life.37,38 High costs related to low back disorders are sustained by employers and
employees.37 Globally, work-related low back pain accounts for 818,000 disability-adjusted life
years lost each year.38 Disability-adjusted life years lost is a measure that represents a more
complete picture of the magnitude of health problems on a population level, making it useful for
health planning.39 These findings taken together indicate there is substantial potential to reduce
low back pain world-wide by reducing occupational risk factors for musculoskeletal injuries.38
The Intersection of Task and Hotel Room Cleaner MSD Injury Risk
Overlap exists among the most ergonomic risk factors for MSD injuries and those frequently associated
with hotel housekeeping tasks: repetitive motions/tasks, bending, extreme reaches, heavy lifting; pushing,
pulling, carrying heavy objects, and prolonged awkward postures.33,34 In addition to the aforementioned
risk factors, forceful exertions, contact stress, excessive work rate, and inadequate recovery time between
housekeeping tasks are also recognized as contributing towards risk of work-related MSDs.1
A biomechanical study as far back as 1992 identified “extreme postures” in occupational
bedmaking as associated with MSD injuries and attributed the trend to use large, heavy beds that
are low in height as possibly increasing MSD risk.40 Subsequent studies by the same authors
confirmed these earlier findings and broke down bedmaking into six isolated tasks: “bedding on,
bedding off, lift middle, lift corner, push bed and pull bed” and made recommendations for
decreasing spinal loading.41,42 The latter study concluded that static methods grossly
13
underestimated the amount of spinal loading and that safe lifting limits could be exceeded during
occupational bedmaking.
Biomechanical analyses of hotel room cleaning work using the Lumbar Motion Monitor (LMM)
found a 79% job risk for a low back disorder as a result of performing hotel room cleaning tasks
overall, a 69% risk from bedmaking tasks and a 66% risk from bathroom tasks.8 The LMM
evaluates the likelihood (risk) that performing a job overall or a specific task may result in a low
back disorder. The LMM uses the following five measures of trunk movement: 1) forward
bending, 2) side-to-side bending, 3) twisting, 4) the force exerted at the moment of lifting and 5)
a lift rate, making it a ‘dynamic’ assessment method.9 Jobs with an overall risk greater than 60%
are high-risk, followed by mid-risk jobs with a risk greater than 30% and less than 60% and
lowrisk jobs are those with risk less than 30%.9 It is important to note that in this evaluation,
none of the hotel room cleaning tasks fell into the low-risk zone (<30%).
The next step beyond estimating low back injury risk by task is to be able to associate tasks with
injury outcomes such as nature of injury and part of body injured. Such an analysis could
contribute new knowledge to target injury reduction efforts by nature of injury, task and part of
body location. These efforts lay the foundation for task-specific worksite interventions. To
perform such an analysis would require reviewing task and injury data from a source that
combines job task information with injury and medical information. For work-related MSDs,
workers’ compensation data is a recommended source, albeit with limitations.
Part 2. Public Health Research Approaches to Injury Control: Application to the
Prevention of Hotel Room Cleaner MSD Injuries and Identification of Research Gaps

14
Theoretical Framework of Injury Control and Risk Reduction
Three frameworks useful for injury prevention and control guided this dissertation: Haddon’s
Matrix, the WHO’s Public Health Approach and the Unified Model put forth by Lett,
Kobusingye and Sethi.
Haddon’s Matrix
Haddon’s Matrix provides the researcher with a framework to look at a variety of potential
causative factors of an injury event instead of only providing a description of an accident with no
thought about etiology.43 From the same article, Haddon points out that descriptions of accidents
have “… a long history and close relationship….to notions of personal vulnerability and
invulnerability.” Haddon’s inclusion of the physical and cultural environments shifts the focus
from solely the ‘host,’ which in the context of occupational injuries is the worker, to focus on the
‘vector’ which is the energy/hazard the worker experiences. From there, then the shift is to the
‘environmental factors,’ namely, workplace (physical) and work organization (cultural). For the
occurrence of MSD injuries to hotel room cleaners, Haddon’s matrix has many applications. For
the vector, also known as the “etiologic agent”, one hotel room cleaning example is the
mechanical force exerted to lift mattresses and the movement of the hotel room cleaner’s trunk
(back) to make the bed as demonstrated by LMM biomechanical evaluations.43 Another example
is the speed with which hotel room cleaners move from one task to another. The physical and
cultural environments are critical factors for the occurrence of MSD injuries to hotel room
cleaners as illustrated in the previous paragraphs about how physically demanding the work is

15
(biomechanical studies, worker surveys) and the intensification of hotel room cleaner workload
due to changes in the hotel industry’s luxury accommodations and business model regarding
staffing.
By focusing on the etiology – the agent (vector) and environmental factors, then you can focus
on what Haddon calls “control opportunities.” These control opportunities present themselves in
the three phases of Haddon’s time dimension. The recognition of control opportunities and the
inclusion of a time dimension sets Haddon’s Matrix apart by establishing that injuries are not
only predictable events but also preventable ones.44 Injury prevention comprises the first phase –
prevention of the etiologic agent reaching the host. For hotel room cleaner MSDs, it is not
possible to prevent the force needed to lift mattresses to make the beds from reaching the hotel
room cleaner. Instead, we look at the second phase that “involves the interaction of the etiologic
agents and the susceptible structures”.43
In phase two, the amount of upper extremity and back exertion is statistically significantly
reduced by using a mattress lift tool and fitted sheets together.45 The mattress lift tool and fitted
sheet in this study are interventions and are examples of focusing on the etiologic agent
(mechanical energy), the physical environment (weight of the mattress) and the cultural
environment (using a flat sheet, more common in hotels, than a fitted sheet). This framework
provides an emphasis on interventions for changing the workplace and work organization and not
solely changing the actions of the host (the worker), e.g., training the worker in safe lifting.

16
Although safe lifting techniques by the worker are important, Haddon’s phase two emphasizes
solutions and creates opportunities for innovation, like using a mattress lift tool with a fitted
sheet reducing the number of mattress lifts from 15 to 7.8 lifts, a 48% reduction in lifting.45
Haddon’s final phase, the third phase, focuses on “maximizing salvage, once damage has been
done to the susceptible structures”.43 It is this minimization of an injury’s damage to the worker
in the third phase where Haddon emphasizes “…..that make the problem [damage to the host] of
social concern….and must be reduced [the damage]. The problem is not a priori “to prevent
accidents” per se.” Based on Haddon’s emphasis, the third phase shifts the focus to reducing the
damage of the injury which would support researchers studying workers’ compensation and
rehabilitation strategies. For example, one study found modified-work programs to be an option
for an earlier return to work which benefited workers categorized as temporarily and
permanently disabled and provided cost savings to the employer.46
Haddon’s Matrix helps to identify important research gaps by breaking down the hotel room
cleaner MSD injury event into etiologic factors and intervention points using the three time
dimensions. Haddon’s Matrix helps to identify important areas of research and possible data
gaps. For example, research exists about the injury experience of the host (hotel room cleaner)
from university and union research efforts and other academic authors but not from other sources
such as government agencies like the Bureau of Labor Statistics and only limited ‘grey’
publications using administrative data such as workers’ compensation claims.5,6,10,11,20,47 For the
second phase that focuses on the interaction of the host with vectors (etiologic agents), when
reviewing the literature, only two peer-reviewed studies identify hazards and solutions to reduce
injury risk factors of hotel room cleaning. A study from 2005 found that a handled shower

17
cleaning tool resulted in more neutral postures for cleaning bathroom showers, although not
specific to the hotel industry, the findings are applicable.48 More recently, a 2019 bedmaking
study found that using a mattress lifting tool and a fitted sheet together significantly reduced the
count of mattress lifts and upper extremity and back exertions.45
As demonstrated above, more studies are needed about interventions specific to tasks performed
by hotel room cleaners that contribute to the risk of MSDs. Breaking down the job of hotel room
cleaning into tasks can lead to identifying 1) cause – the tasks that are high-risk for a MSD injury
and 2) interventions specific to those high-risk tasks for MSDs. Biomechanical studies referred
to earlier using the LMM technology, identify bedmaking and bathroom cleaning as tasks with a
greater likelihood, 69% and 66% respectively, of causing a low back disorder injury.8,9 The
LMM technology is unable to identify risk for other parts of the body besides the lower back. In
a study using administrative data, the back, upper extremities and shoulders were the leading
parts of body affected for hotel room cleaners with MSDs, respectively.10 The role of task and its
impact on upper extremities, shoulders and other possible parts of body requires further study.
The Public Health Approach
The World Health Organization’s (WHO) public health approach is an epidemiological
framework consisting of four hierarchal elements also known as steps: “surveillance; risk factor
identification; designing and piloting interventions, followed by evaluation; and large-scale
program implementation”.49,50 The Public Health Approach, while overlapping with Haddon’s
Matrix about risk factor and intervention identification, adds two population-level components:

18
surveillance and large-scale program implementation. The inclusion of surveillance in the Public
Health Approach is important because it is the first step in defining a public health problem that
affects a population instead of only a specific host and/or a specific event in time. For this
dissertation, the population of interest is hotel room clean workers and their work-related
injuries. Without surveillance data, the effectiveness of carrying out the next population-focused
step – a large-scale program – would be limited, at best or worse yet, may result in erroneous
conclusions and inaccurate subsequent actions in the application step.
My dissertation contributes to the Public Health Approach framework by identifying a population
at risk for MSD injuries - hotel room cleaners. Since my dissertation Aim 1 focuses on
identifying the occupation of hotel room cleaner in workers’ compensation MSD claims data, my
improved research methods identify the population at risk in this data. This enables researchers
to carry out surveillance studies of changes over time in the number, nature of injury, cause of
injury, part of body injured and other variables analyzed in Aim 3 of this dissertation.
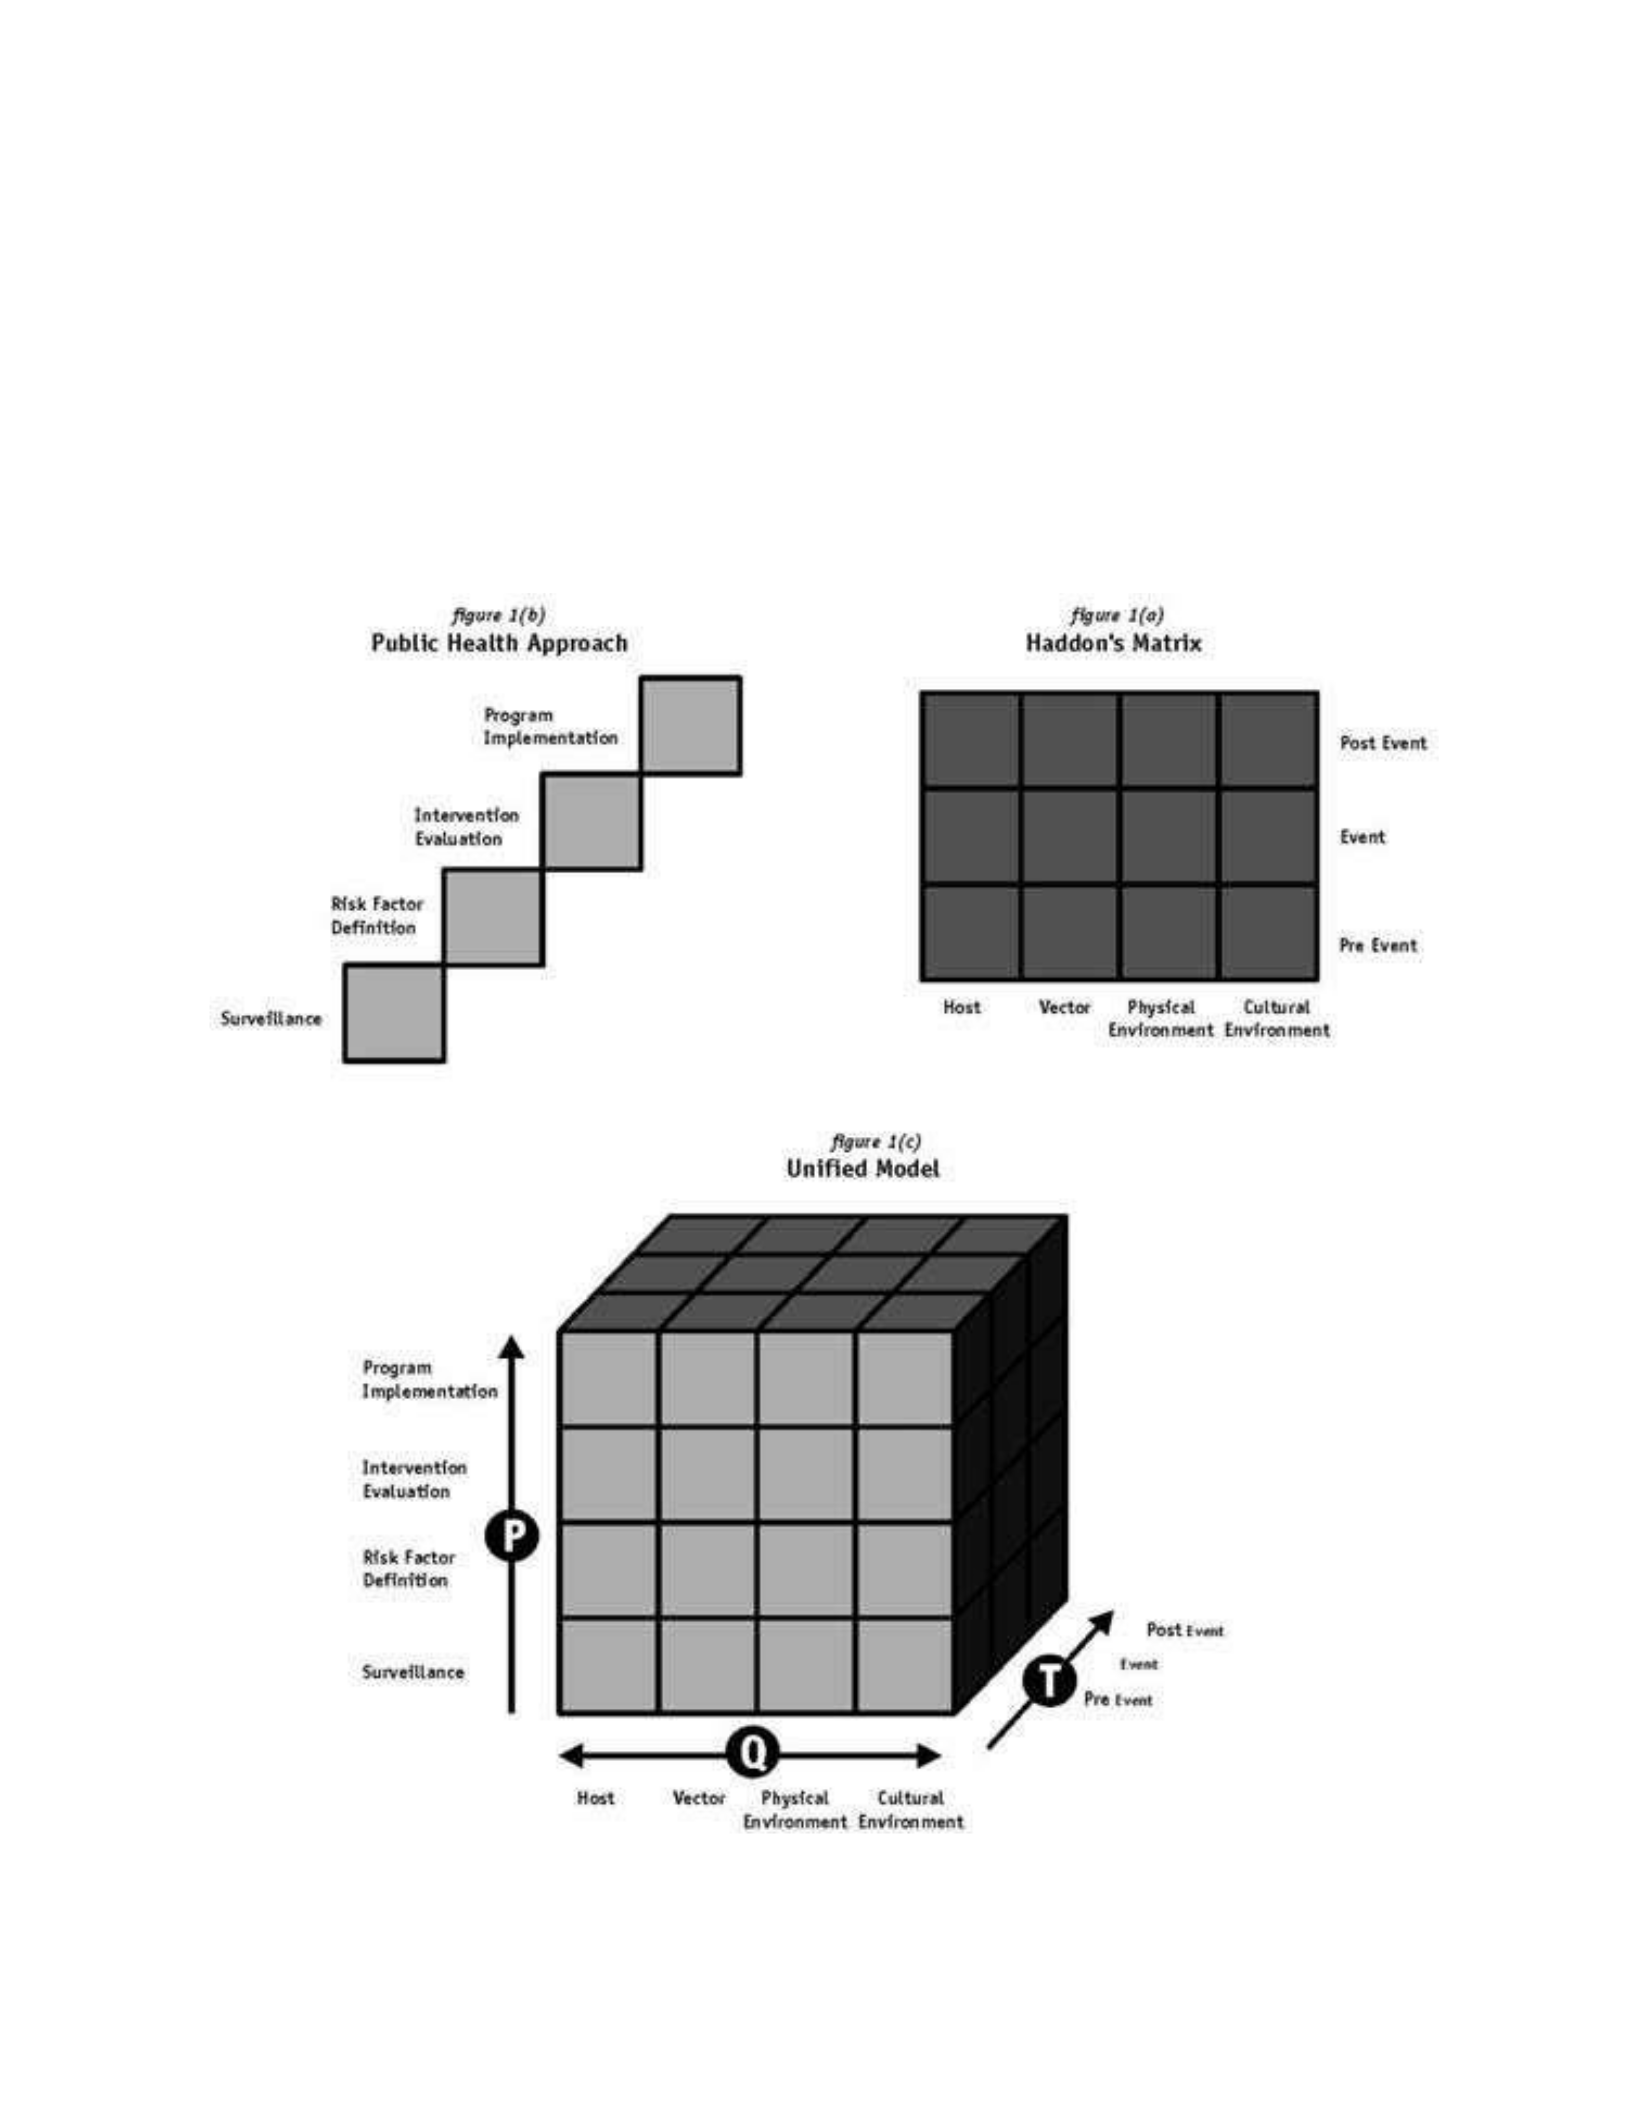
The Unified Model
The Unified Model (Figure 1) combines the Public Health Approach with Haddon’s Matrix (Lett
et al., 2002) and provides a clear construct for injury investigation and science-based injury
prevention interventions. The Unified Model combines the epidemiological elements and ‘injury
as a disease’ concept of Haddon’s Matrix with the Public Health Approach’s focus on scientific
methods to perform necessary surveillance, followed by identification of risk factors and
19
evaluation of interventions before broad implementation. Taken together, the unified model
provides for a comprehensive and precise application of injury control measures and policies.
Figure 1 Unified Model. A Unified Framework for Injury Control: the Public Health Approach and
Haddon's Matrix Combined (Lett et al., 2002)

20
The Unified Model drives the aims of my dissertation, which are to improve research methods to
identify hotel room cleaners and task at time of injury in workers’ compensation claims to access
this data for statistical analyses and thereby contribute reliable information for a comprehensive
and coherent approach to injury control and prevention. This data is needed to counter the failure
by the hotel industry to control the hazards resulting in hotel room cleaner MSD injuries. The
ultimate goal of my dissertation is to develop methods that will aid researchers to produce
science-based evidence necessary for effective intervention development and program
implementation. As Lett et al., point out, without a comprehensive and coherent model like the
Unified Model with its three axes, erroneous assertions at best, false assertions at worst, about
causality and preventive measures can impede (continue to impede) valid interventions and
effective programs for injury control.
The Unified Model, and the select model elements from above, guide the dissertation to answer
the following methodological and research questions:
• Can we establish that as an occupation, hotel room cleaners experience MSD injuries?
• Can we characterize hotel room cleaner MSD claims by demographic factors of the host
such as gender and age?
• Can we characterize hotel room cleaner MSD claims by work-related factors of the host
such as job title category, e.g., housekeeper, maid and job tenure?
• What are the leading nature of injury categories found in the claims data?
• What are the leading cause of injury categories found in the claims data?
• What are the leading part of body injured categories found in the claims data?

21
• Can we characterize hotel room cleaner MSD injuries by task at time of injury?
Workers’ Compensation Surveillance Data: Application of the Public Health Approach
If we review again the four steps of the Public Health Approach: “1) surveillance, 2) risk factor
analysis to identify causes, 3) develop and test interventions, and 4) large-scale program
implementation and evaluation,” we will see that this framework coincides with the use of
workers’ compensation data for my dissertation.44,49,50 Each dissertation aim complements each
step of the framework with the exception of the last step which is beyond the scope of my
dissertation but is clearly an aspiration of my dissertation, namely that my dissertation research
can contribute to implementation of large-scale intervention efforts. Below are examples of how
my dissertation aims complement the first three steps of the Public Health Approach and
contribute towards the fourth step:
1) identify hotel room cleaners as an at-risk occupation for MSD injuries and thereby improve
occupational injury surveillance; 2) provide task at time of injury data to contribute towards
identifying job tasks associated with injury factors and outcomes and provide data for statistical
analyses and 3) perform descriptive analyses to characterize MSD injuries by several factors,
including task at time of injury, to contribute science-based evidence necessary for intervention
development and subsequent injury prevention program implementation. In summary, my
analysis will establish that hotel room cleaners experience MSD injuries, identify tasks
associated with MSD injury factors, and describe MSD injury characteristics. With the new
research methods, occupational injury surveillance using California workers’ compensation

22
claims data of hotel room cleaners will be possible and as interventions are developed, piloted
and evaluated, ideally as part of a large-scale injury control program, their impact can be
measured over time through surveillance efforts including changes in nature and cause of injury,
part of body injured and tasks associated with MSD injuries. Without the research methods to
identify occupation and task at time of injury, the above surveillance, intervention development
and program implementation and evaluation efforts would be impossible or at least seriously
limited or carried out in error. Workers’ compensation data provides information about the
claimant related to their occupation, injury, years worked and disability benefits. Medical billing
data can also be linked to the workers’ compensation data to provide information such as medical
diagnoses, treatment and medical benefits.
Part 3: Workers’ Compensation Data: An Approach to Address Hotel Room Cleaner Injury
Data Gaps
Without surveillance data, it is not possible to substantiate the intersection of MSD injury risks in
the occupation of cleaner with the MSD injury risks in the hotel industry, namely, hotel guest
room cleaning job tasks. This is precisely where the first half of the title of my dissertation
originates: “The Intersection of Industry, Occupation and Job Tasks with Hotel Room Cleaner
Musculoskeletal Disorder Injuries: A Methods Approach to the Analysis of California Workers’
Compensation Data.” It is the lack of surveillance data by the Bureau of Labor Statistics about
the epidemiology (the magnitude, characteristics, rates and trends) of hotel room cleaner MSD
injuries that is an obstacle to intervention development, intervention evaluation and program
implementation as part of injury control and prevention efforts. Workers compensation data –

23
characterization of hotel room cleaner MSD injuries and identification of task at time of injury –
can provide injury details that BLS data cannot and can be used for surveillance with limitations.
Some of these limitations include low rates of workers filing WC claims -- only 25% of workers
with musculoskeletal injuries filed a WC claim and of Las Vegas hotel room cleaners reporting
pain, only 20% filed a claim.7,51 In the latter case, this may reflect low rates of reporting
workrelated pain to employers by hotel room cleaners ranging from 31% to 50% and
discouragement to report pain or file a claim, due to 35% of hotel room cleaner WC claims being
denied.5,7 As a surveillance system, the “capture” rate of upper extremity MSD injuries by the
workers’ compensation system has been estimated at less than 8% when compared to other
sources of data.36 Numerous factors for not filing a workers’ compensation claim have been cited
in the literature, making it necessary to recognize the serious limitations of this data while
utilizing the important information it can provide about occupational injuries.52
The approach that I have chosen to address the data gaps related to MSD injuries and hotel room
cleaners is to use workers’ compensation (WC) claims data and specifically claims from the state
of California. Workers’ compensation records provide data variables such as “industry,
occupation, nature of injury and cause, hospitalizations, medical treatments and costs, disability
duration…”, among others, that comprise a robust database of information provided by
employers, healthcare providers and insurance companies.53 NIOSH’s Center for Workers’
Compensation Studies recommends WC research activities for the purposes of “supporting
primary-prevention efforts, developing interventions to improve safety, and evaluating the
primary-prevention effects of public policy toward workplace safety (such as OSHA
enforcement, OSHA regulations, and targeted safety interventions)”.54

24
Application of Workers’ Compensation Data for Task Analysis of Hotel Room Cleaner
Musculoskeletal Disorders
WC analysis at the task level could provide insight into the cause of injury and contributing
factors. WC data is a source of narrative text information for a specific industry and/or
occupation that potentially can be distilled down to the tasks associated with a certain nature of
injury and the circumstances at the time of the injury.
More directly relevant to the topic of this dissertation is a task analysis performed by the
California Division of Occupational Safety and Health on a subset of data from a study of hotel
room cleaner MSDs using 2009-2012 claims data from California’s Workers’ Compensation
Information System.11,47 In a manual review of a sample of 2,000 hotel room cleaner MSD
claims cases, task was identified in 66% of cases reviewed and five broad task categories were
identified – bedmaking, bathroom cleaning, vacuuming/room cleaning, cart handling and other.
Next, Neidhardt reviewed over 7,000 MSD hotel room cleaner claims cases and was able to
break down task categories further into subtasks such as scrubbing the tub as part of the
‘bathroom cleaning’ category. Although challenges exist for identifying occupation and task in
California workers’ compensation data, there remains significant potential for using this data for
injury control.11,47 Research is needed to improve accessibility to this information in claims data.
California Workers’ Compensation Data: A Priority for Hotel Room Cleaner MSD Injury
Research
There are several reasons for making California a priority when selecting state workers’
compensation data for research about this specific workforce. California is the state with the
25
highest employment of Maids and Housekeepers – with 101,370 employed in all industries as of
May 2019 shown in Table 1.2.13 In 2017, California ranked first among all U.S. states in the
amount of total workers’ compensation benefits paid, totaling $12.1 billion.55
Table 1.2 Five States with the Highest Employment Level for Maids and Housekeeping
Cleaners. Occupational Employment and Wages, May 2019. Bureau of Labor Statistics
To understand the scale of the number of WC claims filed annually in California, over 680,000
First Report of Injury Forms (FROI) were filed in 2019 as part of workers’ compensation
claims.56 Moreover, California is the only state with a hotel room cleaning musculoskeletal
injury prevention standard, which took effect on July 1, 2018; a pressing need exists for baseline
data about these injuries using the states’ Workers’ Compensation Information System.1
Exploration of Methodological Issues in Workers’ Compensation Data: Filling Research
Gaps
Employment o
f Maids and Housekeeping
Cleaners, by State, May 2019.
State
Employment
California
101,370
Florida
80,000
Texas
76,040
New York
47,990
North Carolina
32,530

26
Using California workers’ compensation injury claims data, the goals of this dissertation are to
identify and describe work-related musculoskeletal injuries occurring to hotel room cleaners
from 2007-2016 and identify task at time of injury from 2012-2016 to explore the relationship
between task and injury outcomes, e.g., nature of injury and part of body injured. In order to
accomplish these goals, existing research methods were evaluated and modified and new
methods were created and tested. The aims of this study address these areas of future research
important for injury prevention and control, worksite interventions and occupational injury
surveillance. The first two aims test research methods for identifying: 1) the occupation of hotel
room cleaners in hotel worker MSD injury claims data and 2) the task associated with the hotel
room cleaner MSD injury incident. The third aim examines the findings of descriptive analyses
that characterize hotel room cleaner MSD injuries utilizing select variables drawn from the data
extraction from California’s Workers’ Compensation Information Systems listed in Appendix E,
provided to the principal investigator by California’s Department of Workers’ Compensation.
This dissertation is a Proof of Concept study as it tests the feasibility of using modified or new
research methods to identify hotel room cleaner MSD claims and task at time of injury in a
dataset of WC hotel worker MSDs. Information in Section 3 Methods details the application of
previously validated occupation and task terms from other studies to the custom extraction that
created the dissertation administrative dataset and compares the results (evidence) of improved
and/or new research methods. Proof of Concept studies have been useful in administrative data
studies by demonstrating the feasibility of applying varying methods such as term extraction to
free text data in medical records, the use of validated algorithms for identifying multiple
morbidities for chronic disease surveillance and testing the efficacy of data linkage systems

27
across state and national jurisdictions to study healthcare outcomes of injury-related
hospitalizations.57-59 More recently, natural language processing techniques were found to be
useful in coding interviews with public health content, either as a first step in coding text data or
as an accuracy check after coding was completed.60 A Proof of Concept approach to evaluate the
potential of natural language processes in combination with human coding was appropriate to
access narrative next data in workers’ compensation claims and to improve research methods for
the purpose of quantitative analyses.
Dissertation Aims
The three aims of this dissertation research are:
Aim 1: To create a new variable ‘Hotel Room Cleaner’ by testing and modifying existing
methods to identify hotel room cleaners in the narrative text field for ‘occupation’ using pooled
2007-2016 California workers’ compensation claims data for hotel industry workers with
musculoskeletal disorder (MSD) injuries. This creates the dissertation dataset comprised of hotel
room cleaner MSD injury claims. This data is needed for analysis in Aim 3A and also provides
the data from which a task sample is created for analysis in Aim 3B.
Aim 2: To develop and test methods to create a new variable that identifies the task associated
with the hotel room cleaner MSD injury incident using narrative text information from the
‘injury description’ field in claims data for a subsample of the dissertation dataset. Identifying
task will provide the data needed for analyses in Aim 3B from 2007-2016 and contribute towards
intervention-related research.

28
Aim 3: To perform basic descriptive statistical analyses to characterize hotel room cleaner MSD
injuries by nature of injury (e.g., sprain or strain), cause of injury (e.g., lifting or pushing or
pulling), part of body injured, age, job tenure, and task at time of injury.
Aim 3A: To perform descriptive statistical analyses to characterize MSD injuries in hotel
room cleaners by demographic (age, gender), injury (nature, cause, cause of injury
category, part of body, part of body category) and work (tenure) variables.
Aim 3B: To perform three descriptive statistical analyses to characterize hotel room
cleaner MSD claims stratified into seven broad task categories by injury characteristics:
1) nature of injury, 2) cause of injury and 3) part of body.
In carrying out the dissertation aims, different elements of the three axes of the Unified Model
were applied: ‘T’ for time elements; ‘Q’ for epidemiologic elements (disease concepts); and ‘P’
for Public Health Approach elements (systematic science-based methodology). The integration of
my aims with the three axes is summarized below:
Aim 1: Identification of hotel room cleaner occupation in California workers’ compensation
MSD claims data.
Unified Model Element: Axis P - Surveillance, Axis Q – Host.
Aim 2: Identification of task at time of injury.
Unified Model Element: Axis P - Risk Factor Definition, Axis Q - Vector, Axis T - Event.

29
Aim 3: Descriptive statistical analyses to characterize MSD injuries by nature of injury (e.g.,
sprain or strain), cause of injury (e.g., lifting or pushing or pulling), part of body injured, age, job
tenure and task at time of injury.
Unified Model Element: Axis P - Risk Factor Definition, Axis Q - Host, Axis Q -Vector, Axis T -
Event.
Dissertation Sections
Section 1 introduces the public health issue of concern, namely, musculoskeletal disorder injuries
occurring to hotel room cleaners. Background is provided that contributes to theories of
causation of the MSDs by describing the changes in the hotel industry’s guest room
accommodations, resultant intensification of hotel room cleaning workload and associated
prevalence of workplace pain and injuries. This section also puts forth a framework for the use
of public health research approaches for injury control to prevent hotel room cleaner
musculoskeletal disorders in light of research gaps. The potential of workers’ compensation data
to address those data gaps is demonstrated.
Section 2 builds on the literature referenced in the introduction section to support the aims,
research questions and selection of workers’ compensation data for my dissertation research. In
this section, a thorough review of the literature is provided that demonstrates gaps in
occupational injury surveillance systems that fail to identify injured hotel room cleaners, the lack
of scientific evidence about interventions to prevent MSD injuries occurring to hotel room
cleaners and the inaccessibility of narrative text data in workers’ compensation claim databases

30
for injury and task information. The literature review critiques what data is needed and argues for
innovative research methods to bridge existing data gaps.
Section 3 describes the methods used to identify the occupation of hotel room cleaner (Aim 1)
and the task at time of injury (Aim 2) from narrative text data. This section identifies the
challenges of testing and modifying existing methods and creating new ones with innovative
artificial intelligence techniques of natural language processing and text classification models.
Section 4 explores the MSD data by performing descriptive analyses (Aim 3) in two parts. The
first part (Aim 3A) describes the MSD injuries by the following variables: demographics (age,
gender), injury characteristics (nature, cause, cause of injury category, part of body, part of body
category) and work descriptors (job tenure at time of injury, hotel room cleaner job title). The
second part (Aim 3B) stratifies the MSD claims into seven task at time of injury categories and
describes the data by the following injury characteristics: 1) nature of injury, 2) cause of injury
(lifting, carrying, twisting, etc.) and 3) part of body.
In Section 5, the study findings are discussed along with the study’s strengths and limitations.
The public health significance is presented. Conclusions based on a critical review of the study’s
aims and methodology are offered. Policy implications and recommendations for areas of future
research are put forth. Potential worksites interventions are suggested based on study findings.
Section 2: Literature Review

31
Utility of Workers’ Compensation Data for Identifying Occupation and Task for Injury
Analysis
Numerous studies using WC data succeed in identifying the leading types of injuries (nature of
injury), the factors contributing to the cause of injury and parts of body affected stratified by
industry; by occupation; by injury type at the state level, by part of body and occupation, for
example 25% of WC claims by welders concerned eye injuries and helpers/laborers had eye
injury rates twice that of workers overall; and by injury type and occupation.61-68 WC data can
identify categories of workers not easily accessible in administrative datasets due to the nature of
their employment. Multiple approaches using California WCIS data identified residential
workers employed by private households by identifying tasks associated with day laborer work,
e.g., maintenance and landscaping and domestic work, e.g., housekeeping and childcare.69
Findings from unpublished studies explored methods of defining MSDs and occupation using
WCIS data for hotel housekeepers and analyzing by task.11,47 Leading cause of injuries were
strain or injury, NOC; pushing or pulling; lifting; and repetitive motion, with the low back area
and shoulders the leading parts of body injured.11
Workers’ compensation claims data can provide layers of information that, with further research,
will uncover high-risk industries, operations, and occupations, along with corresponding hazards,
injuries and parts of body affected. These findings can then lead to the discovery of high-risk
tasks. An investigation of agriculture workers using four years of workers’ compensation data
from Colorado identified that the largest proportion of injury claims were due to livestock-

32
worker interaction.70 For these claims, the leading nature of injury was contusions occurring to
the upper and lower extremities. Douphrate and co-authors followed up these findings with a
study focusing on livestock-handling injuries only using ten years of WC data.71 Study results
found dairy farms having the second highest injury claim rate compared to the two other
employers studied, “cattle dealers and cattle/livestock raisers”. Narrative text injury descriptions
from WC claims detected that 48% of the animal-related injuries occurred in the dairy parlor. By
identifying the location of where the injuries occurred on a dairy farm (dairy parlor), then the job
task (milking) was identified. In the proceedings from a 2012 NIOSH-sponsored conference on
the research applications of workers’ compensation data, conference facilitators concluded that
“best practices for the use of workers’ compensation data to identify intervention needs could be
developed”.72 One underlying assumption is, having reached the threshold of a workers’
compensation claim, these injuries resulted from high-risk tasks. This assumption is supported by
studies that found an increased likelihood of workers filing a workers’ compensation claim is
associated with: work-relatedness confirmed by a physician, involved surgery and/or days away
from work; high levels of pain and high physical job demands; and restrictions on physical
activity, decreased health status, days away from work equal to or greater than a week.36,51,52
Implementing recommended interventions based on these cases is a priority.
Task Analysis: Pathway to Interventions
Task analysis has identified potential intervention points for varying industries and occupations.
Analysis of narrative text data from WC claims of hospital workers categorized patient handling
injuries into seven subtasks with 40% occurring from either lifting or transferring the patient and

33
32% from repositioning, pulling or catching the patient.73 By pinpointing the task and the
prevalence of injuries associated with that task, researchers identified interventions appropriate
for the task and prioritized them by greatest need.
Task analysis can be used more readily to identify the maximum workload of an overall task or
the workload of a single task.74 Task analysis, triggered by research involving workers’
compensation claims, can evolve over time with each new study building on the findings of
earlier studies and thereby creating a trajectory of data analysis, hazard assessment, intervention
development and evaluation, program implementation and potentially, policy initiatives. This
trajectory echoes the theoretical framework of my dissertation, the Unified Model, that ranges
from “surveillance to risk factor identification, followed by intervention evaluation and program
implementation.”44
Example of the Unified Model Put into Practice: Dairy Parlor Milking Task Research Further
research by Douphrate and colleagues exemplifies the above trajectory and is presented here as
an example. Increasing trends in dairy farming towards large herd operations in the U.S. resulted
in the industrialization of parlor milking systems and milking practices, raising concerns about
ergonomic hazards and the lack of solutions beyond stop-gap measures, e.g., lighter equipment,
rubber mats.75,76 Research identified high-risk milking practices affecting the upper extremities,
that were then associated with differences in the configuration of large herd dairy parlors.77,78
Symptoms of work-related MSDs in the upper extremities (shoulders and wrists/hands) were
found for 80% of workers studied in large-herd dairy parlors and were associated with working
conditions, primarily static postures, repetitive tasks, lack of breaks, extended reaches and

34
working while injured.79 In the course of developing milking task interventions, five main
milking tasks were identified, with attachment of the milking unit to the cow’s udder as the most
physically demanding.80 Study authors focused on the hazards of the milking unit (equipment)
and identified several features e.g., weight, spread of the milk tubes, shape of the teat cup, that
suggest possible varying levels of corresponding muscle activity. The authors call for design
changes, identified with the help of worker input, to reduce worker muscle fatigue, noting that
for milking tasks that were highly repetitive, small reductions in muscle loading over time could
delay or prevent the progression of MSD injuries.
The lack of occupational safety and health regulations targeting the agriculture industry in
general and dairy farming in particular contribute to the existence of unsafe working conditions
in the dairy industry.81 A review of sixteen intervention studies in the dairy industry found that
none were of sufficient sample size to evaluate their impact on injury rates.82 The researchers
propose strict evaluation methods be included in study design, beyond measuring knowledge
gained. Also, to improve safety climate, transformational leadership is needed that integrates
worker health and safety in dairy management’s plans along with other goals, e.g., production.83
This research trajectory serves as an example for other industries about the potential of WC data
to trigger intervention studies.
Task Analysis of Hotel Room Cleaner Occupation
Ergonomic task analysis involves “… defining the problem, analyzing problem jobs and
implementing ergonomic solutions”.84 Identifying work areas and jobs, compiling list of job

35
duties or job description and determining job exposures is a first step as part of analyzing jobs
before selecting the method for task analysis and performing the task assessment.84
Biomechanical evaluations using the Lumbar Motion Monitor (LMM) of hotel room cleaning
work, referred to earlier, generated broad task categories and corresponding specific subtasks
(Appendix A) as part of enumerating risk levels for the likelihood that a task results in a
workrelated low back disorder. Hotel room cleaner task lists serve as a framework for
intervention points for reduction of injury risk.9 Allread et al’s three main task categories are
“Bedmaking”
(seven subtasks), “Bathroom cleaning (six subtasks)” and “Other” which includes vacuuming,
dusting, replenishing from cart and checking furniture and drawers. Based on three hotel room
cleaning evaluations at different hotel properties, there was no single subtask considered in the
“low-risk” category for a low back disorder. The results of all three evaluations for the hotel
room cleaning job overall were in the “high-risk” category. Neidhardt manually reviewed 2,000
WCIS claims after excluding 665 (25%) due to lack of job task information associated with the
injury. Neidhardt used these task categories for WCIS data analysis: “Cleaning bathrooms,
shower-tub, mopping floors”; “Making bed, lifting mattress, moving-rearranging bed”;
“Vacuuming, spot cleaning floor, room cleaning”; Pushing or pulling cart, sudden stop of cart, re-
stocking cart”; “Injuries associated with stairs, steps, ladders”; “Other”. The leading four tasks at
time of injury were bedmaking, bathroom cleaning, stairs/steps/ladders and pushing or pulling
cart, respectively. For each task categories, there were 4-5 subtasks. For example, pushing or
pulling was the task associated with the injury for “vacuuming”; pushing on carpet for “operating
linen cart”; bending to clean for “cleaning tub or shower”; pulling changing linen for “handling

36
linen”; and tucking under or lifting mattress for “handling a mattress”. These findings are
supported by Allread et al’s LMM evaluations that identify lifting rate and forward bending as
key risk factors for low back injuries in hotel room cleaners.9 Allread et al found the following
hotel room cleaning tasks to be “high-risk”: bedmaking, vacuuming, bathroom cleaning and
dusting.9 A peer-reviewed study echoes the above findings and to date, is the only one that
associates specific hotel room cleaning tasks with self-reported hotel room cleaner ergonomic
problems.6 Survey results by Krause et al found the following leading concerns .. “linen cart too
heavy (84%), heavy bedspreads, or comforters on beds (74%)” and …“vacuum cleaner too heavy
(62%) and vacuum cleaner needs repair (62%).”
Interventions exist for musculoskeletal injury risk factors of bathroom cleaning with scientific
findings from over fifteen years ago. Researchers found that a 21-inch long handled cleaning tool
provided a more neutral work posture for the wrist, shoulders and trunk compared to using a
sponge.48 In addition, awkward postures of the lower extremities were reduced: there was less
climbing into bathtubs and less kneeling to clean bathtubs. This resulted in safer foot placement
and less wear and tear on the knees. A Cal/OSHA publication also released in 2005, “Working
Safer and Easier for Janitors, Custodians and Housekeepers,” is an eighty-six-page manual of
valuable information, illustrating tools and safe work practices for cleaners using ergonomics for
injury prevention.85 These include fitted sheets, long-handled tools and safe work practices for
moving furniture and lifting mattresses. To date, only one intervention study exists
recommending bedmaking aids and fitted sheets which together were found to reduce lifting by
48%.45

37
With limited injury data on the task, cause of injury and part of body injured specific to
performing hotel room cleaning work, it is less likely that employers will invest in programs
applying existing interventions or exploring the development of new ones when there is a lack of
administrative data documenting the outcome of work-related job hazards, namely occupational
injuries. Regulations can help employers focus separate job tasks, identify risk factors and
develop programs to put into practice solutions such as worksite interventions. Hotel room
cleaner tasks are defined in Cal/OSHA 3345 Hotel Housekeeping Musculoskeletal Injury
Prevention standard (Appendix B) as “… [those]…related to cleaning and maintaining sleeping
room accommodations”… “include, but are not limited to, the following: (1) sweeping, dusting,
scrubbing, mopping and polishing of floors, tubs, showers, sinks, mirrors, walls, fixtures, and
other surfaces; (2) making beds; (3) vacuuming; (4) loading, unloading, pushing, and pulling
linen carts; (5) removing and supplying linen and other supplies in the rooms; (6) collecting and
disposing of trash; and (7) moving furniture”. California’s promulgation of this regulation, the
only state to do so, requires employers to implement an MSD injury control plan for hotel room
cleaners defined as “…. an employee who performs housekeeping tasks and may include
employees referred to as housekeepers, guest room attendants, room cleaners, maids, and
housepersons.” Plan elements include performance of a worksite evaluation, injury investigation,
identification of solutions, worker and supervisor training, and the active participation of workers
and their union representatives.1
The Potential of and Challenges to Using Narrative Text Data
Similar to the various uses for WC data for occupational injury research targeting occupation and
task, studies using narrative text data vary in their purpose, e.g., text extraction, validation of

38
coded data; by approach/technique; and by method of quality control assessment, with complete
information detailing the latter two elements lacking.86 In a review article of 28 peer-reviewed
papers, among the authors’ conclusions, use of systematic methods to search narrative text data
provided important information not previously accessible in coded data and computerized
methods can be effective to classify less complex data into categories, saving complicated text
for manual methods.86 Identification of tractor overturns as a cause of injury for tractor fatalities
increased from 49% using standardized surveillance codes to 54% when incorporating narrative
text data as part of Kentucky Fatality Assessment and Control Evaluation (FACE)
investigations.87 By providing more comprehensive information than the standardized variables
in the FACE dataset, a logistic regression analysis of the narrative text data found increased odds
of workers “dead at the scene” when driving a tractor in “muddy conditions” (OR: 9.1, p<0.01)
and driving a tractor “with a front loader attached” (OR: 5.8, p<0.02). These findings detected
new contributing factors and were added as variables in the FACE program. The limitations of
the data include injury scenarios with sample size too small to be included due to lack of power
for statistical analyses. Combining pre-coded data (gender, industry) with results from coding
injury narratives in WC claims allowed for identifying electrical injuries not commonly
associated with certain industries with electrical hazards, e.g., services (33.4%) and with the
female workforce (27.7%), drawing attention to a probable lack of safety trainings for at risk
workers.88 These same injury narratives provided robust findings about the cause of electrical
injuries when the authors applied case-selection algorithms using pre-coded cause of injury data
variables and a tailored six-category taxonomy to the “accident” and injury narrative
descriptions. The taxonomy included activity, source, initiating process, mechanism of injury,
vector and voltage, providing new insights into non-fatal electrical injuries such as 55% occurred

39
during manual tasks and 24% had appliances and office equipment as the leading source, with
the exception that no information on vector was found.
Yamin et al (2016) created a systematic multi-level classification procedure to decide to which of
three categories a claim belonged using de-identified WC data (n = 4,268) from metal fabrication
employers.89 Study researchers removed claims with MSDs and slips /trips/falls using a keyword
auto-coding program, with “all other injuries” the only claims remaining. This category
accounted for 68% of all claims. The remaining claims were classified by two coders into three
categories: machine-related, non-machine related and possible machine-related. After achieving
83% agreement on the initial coding, the remaining claims were resolved jointly and the potential
machine-related claims were excluded along with the non-machine claims. Using job tasks from
previous hazard evaluations, eight task categories were defined and narrative text descriptions
were manually classified, with 36% (n = 1,053) being machine-related and the rest of the injuries
occurring during secondary tasks. The authors identified that serious injuries, e.g., amputations,
fractures, severe lacerations occurred at various points in the work process, not in only one task,
pointing to a need for broader injury control efforts.
Researchers found the need for guidelines for standardizing text entered into injury descriptions
in order to accurately classify the data.86 Emergency room reports had a high occurrence of word
variation belonging to two groups: 1) spelling errors (11-18.8%), including multiple errors in
each instance and 2) word truncations, abbreviations, acronyms (>20%), with varying success of
different text normalization methods.90 Similar word variation issues were found in other studies
mentioned earlier.87,88

40
Researchers utilized and/or created various methods to improve or ensure the validity of study
results. Lack of sufficient information to identify underlying causes was a limitation of WC data
when used alone, but in conjunction with pre-coded data and a coding taxonomy tailored to the
study objectives, e.g., etiology of injuries, WC data provides useable information.88,89 Using
California WC data, Riley and Mujano created an index measuring the researchers’ confidence
level on employment status of the claimant.69 The index counted the number of sources in the
WC data that indicated the claimant was a residential worker including the narrative text fields of
Occupation and Injury Incident Description fields, finding 14.3% of claims with a high
confidence level and 85.4% with moderate level. Using NIOSH’s Industry and Occupation
Computerized Coding System computerized auto-coder to add 2010 Census Occupation Codes,
numerous occupations at risk for carpal tunnel syndrome were able to be identified using CA
WCIS data.91
Application of AI/Machine Learning Methods to Public Health Research
Semi-automated review, human and machine-combined and natural language processing (NLP)
techniques are increasingly utilized for public health research.60 Occupation injury research leads
the field, accounting for 46% of papers summarized in a systematic review of machine learning
processing methods (MLP).92 Vallmur points to the ability of MLP methods to accurately classify
text data into broad categories, to identify injury patterns and causal mechanisms. A semi-
automated method classified WC narrative text data for 15,000 claims by BLS event codes:
68% using Naïve algorithms only and 32% manually for more challenging narrative data.

41
Maximum accuracy rates for the classified data was 87%.93 These same researchers in a
following study proposed human-machine pairing as a best practice for filtering large
administrative datasets like workers’ compensation claims.94 An important first steps is to have
multiple coders of the narrative text data using a statistical scoring system to resolve
differences.60 Authors of this study recommend computerized methods applied to data where
there is a high confidence level that the data is classified correctly and to enhance computerized
methods with manual coding. For narrative data classified by the model, a best practice resulting
in a relatively high level of accuracy, is to manually code the classified data with the 30% lowest
predictive probabilities and perform computerized coding for the remaining 70% of the data.94
Also, study authors found that algorithms succeeded in coding repetitive, simple narrative text
consistently in a systematic manner. The use of training data and multiple iterations to fine-tune
the model is advised.93 Natural language processing techniques can be combined with human
coding to: verify the accuracy of manually coded data or to classify the data and then use the
NLP findings to generate codes.60 The quality of the source data is key since the model and
algorithms are dependent on the data, impacting the generalizability of applying the model.92-94
Vallmur pointed to data consisting of small sample sizes or specific content areas as limits to the
generalizability for application to other populations as the data influences the models ability to
recognize patterns and those patterns reflect the study population only.92
Section 3: Methods

42
Study Design
This study is a quantitative retrospective record review of administrative data from the California
Workers’ Compensation Information System (WCIS) that describes the frequency of
musculoskeletal disorders (MSDs) among hotel room cleaner claimants and assesses the
association between type and frequency of MSDs and the job task performed at time of injury. In
addition, artificial intelligence (AI) methods were applied to identify narrative text data extracted
from the WCIS dataset, demonstrating the feasibility of utilizing natural language processing
(NLP) techniques to transform narrative text data into coded data suitable for quantitative data
analysis. As a result, two categories of data – occupation and task at time of injury – were joined.
Analysis of this data along with demographic, work, and injury information about MSDs
occurring to hotel room cleaners is now available for public health injury prevention and control
efforts. This information contributes to filling the data gap explained in Section 1 regarding the
lack of published U.S. government occupational injury surveillance data about maid and
housekeeping cleaners employed by the hotel industry. Natural language processing techniques
provided systematic, valid, and replicable methods to filter thousands of WC claims to identify
occupation and task in narrative text data and code the claims swiftly (Appendix I). This proof of
concept study using natural language processing techniques, combined with human coding,
increased the accessibility of narrative text data in injury incident descriptions of administrative
data.60 The methods applied in this dissertation are innovative and contribute towards improving
research methods for the quantitative analysis of workers’ compensation claims. This
combination of NLP techniques and human coding was exemplified in the working relationship
between the AI contractor and myself. Their work was guided by my coding parameters and
algorithms, based on decisions I made in response to challenges in the data, e.g., over two

43
thousand occupation terms from which to differentiate those pertinent to hotel room cleaner job
duties; categorizing task data when generic terms such as “cleaning” or “regular duties” were the
only task terms included in the injury descriptions; distinguishing between a “task” and an
“activity” in the injury description – whether moving a bed is a “moving furniture” task or an
activity within the “bedmaking” task. These decisions were the result of different methods I
applied (detailed in this section) and my expertise acquired from over fifteen years of combined
experience working for the leading hotel workers’ union in North America. First as a hotel
housekeeping injury researcher (four years) and then as director for health and safety (11+ years)
Working with artificial intelligence (AI) experts, my parameters were incorporated into their
model, based on the limits of the NLP techniques, the data and the study timeline.
Data Source
The California Department of Industrial Relations’ Division of Workers’ Compensation (CA-
DWC) provided the secondary data for this study from its Workers’ Compensation Information
System (WCIS), an administrative database of claims. WCIS data includes coded and narrative
text data about an injury or illness, affected employee (including demographic characteristics)
and employer.
Occupational Injury and Illness Data Information Forms: Sources of WCIS Data Elements
In California, when a work-related injury occurs, employers are required to submit either an

44
“Employer’s Report of Occupational Injury or Illness” or a “Doctor’s First Report of
Occupational Injury or Illness” (DFR) to its insurance claims processor. The Doctor’s First
Report form (Appendix C) includes information about the employer and details about the
injury/illness incident, physical examination, test findings, diagnosis and treatment).95 The
Employer’s Report of Occupational Injury and Illness form (Appendix D) includes information
about the employer, the employee’s employment history, wages and hours, injury circumstances,
age, gender, and injury severity. Information from either form fills the “First Report of
Occupational Injury and Illness” submitted electronically by the claims administrator to the CA-
DWC’ Workers’ Compensation Information System within ten working days after learning of
the claim.96
Data Elements of the WCIS Database
The First Report of Occupational Injury and Illness (FROI) completed by the employer’s
insurance claim administrator described above comprises the data elements in the WCIS
database. Data is coded using the terminology, rules and codes from the Workers’ Compensation
Insurance Organization (WCIO) found in Appendix H.
Data Collection
Data Extraction from California’s Division of Workers’ Compensation
The California Division of Workers’ Compensation (CA-DWC) provided a custom data
extraction based on my data request which was prepared with input from subject matter experts,
including those from the California Department of Industrial Relations (CA-DIR) and the

45
CADWC.† I also submitted a data matrix that listed the research justification and corresponding
study aim for each of the requested sixty-five data elements (Vossenas Dissertation WCIS Data
Matrix, Appendix E). A Memorandum of Understanding was signed between the City University
of New York on behalf of the Graduate School of Public Health and Health Policy and
California’s Division of Workers’ Compensation. The last WCIS data file was transmitted
electronically from CA-DWC on 6/27/19. The City University of New York University
Integrated Institutional Review Board approved this study on February 11, 2019 (Appendix F).
Data Sample
WCIS Administrative Data Sample – Hotel Industry Musculoskeletal Disorder (MSD) Claims
This dissertation focuses on coded and narrative text injury and demographic data of California
workers’ compensation claims subsetted from a WCIS administrative data sample for years 2001
through 2016 for hotel industry workers with work-related musculoskeletal disorder injuries.
Sixteen years of data were requested to provide a sample size large enough to generate a
sufficient number of records to: 1) identify the occupation of hotel room cleaner, recognizing that
this job title accounts for about 23% of the hotel workforce; 2) identify the task at time of injury
using seven task categories, recognizing that previous research coded task as “unknown” for
33% of WCIS cases studied, and 3) provide disability and medical billing data associated with
the claims in the study dataset, recognizing that only 47% of claims are estimated to have
medical billing data.47 Study years were limited to begin in 2001 as the WCIS database was
created in mid-2000.

46
Based on discussions with California workers’ compensation subject matter experts, the
following First Report of Occupational Injury (FROI) data elements were considered to be highly
populated and were included in the data extraction: date of injury, nature of injury, part of body
injured, cause of injury, accident description/cause, date of hire, and gender. These data elements,
along with “Occupation,” “Date of Birth” and “Date of Return to Work” comprised the essential
data elements of the study dataset.
Hotel Industry Definition
All claims in the study dataset were for individuals employed in occupations in the
hotel/motel/casino industry referred to throughout this dissertation by the all-encompassing term
“hotel industry.” The hotel industry was defined using industry source codes: two Workers'
Compensation Insurance Rating Bureau (WCIRB) Class codes, ten Standard Industrial
Classification (SIC) codes and four North American Industrial Classification System (NAICS)
codes (Appendix G). No information about employers or worksites were requested.
Musculoskeletal Disorder Case Definition
The CA-DWC used a combination of Worker Compensation Insurance Organizations (WCIO)
codes for the case definition for an MSD injury (Appendix H). I provided this definition in the
data application to the CA-DWC and in subsequent communications with the agency’s data
programming staff. This definition follows methods used with WCIS data for hotel room cleaner
MSD injuries by Cohen et al and replicated in a study about patient handling MSD injuries of
healthcare workers.11
47
The MSD injury case definition requires that a claim includes: one of the specified nature of
injury subcategories, plus one of the specified cause of injury subcategories, plus one of the
specified parts of body injured subcategories. Every claim included in the WCIS sample contains
at least one specified subcategory of each of these three variables in Figure 3.1.
Figure 3.1 Injury Variables that Comprise the Definition of an MSD Injury
Cause of Injury Part of Body
Variable:+ + Injured
Variable: Specified
Subcategories Specified
Subcategories
The specified subcategories by type of variable are listed below:
1. Nature of Injury Specified Subcategories and Codes. Dislocation (16); Hernia (34);
Inflammation (37); Sprain (49); Strain (52); All other specific injuries, NOC (59); All Other
Occupational Disease Injury, NOC (71); VDT-related Disease (76); Carpal Tunnel Syndrome
(78); All Other Cumulative Injury, NOC (80); Multiple Physical Injury Only (90); Multiple
Injuries Including Both Physical and Psychological (91). The definitions of the nature of injury
categories are available via a link in Appendix H. For example, “Sprain (49)” is defined as
“49. Sprain or Tear Internal derangement, a trauma or wrenching of a joint, producing pain and
disability depending upon degree of injury to ligaments” and “Strain (52)” is defined as “52.
Strain or Tear Internal derangement, the trauma to the muscle or the musculotendinous unit from
+
Nature of Injury
Variable:
Specified
Subcategories

48
violent contraction or excessive forcible stretch. 53. Syncope Swooning, fainting, passing out, no
other injury” (Nature of Injury, Appendix H).
2. Cause of Injury Specified Subcategories and Codes. Strain or Injury By: Twisting (53),
Jumping (54), Holding or Carrying (55), Lifting (56), Pushing or Pulling (57), Reaching (58),
Using Tool or Machinery (59), Strain or Injury by, NOC (60), Wielding or Throwing (61),
Repetitive Motion – Carpal Tunnel Syndrome (97); Striking Against or Stepping On: Sanding,
Scraping, Cleaning Operations (67); Rubbed or Abraded by: Repetitive Motion (94), Rubbed or
Abraded, NOC (95); and Miscellaneous Causes: Cumulative, NOC (98) (Cause of Injury,
Appendix H).
3. Part of Body Injured Specified Subcategories and Codes. Neck: Codes 20-23, 25; Upper
Extremities: Codes 30-39 (all codes); Trunk: Codes 40-47 (all codes), 61-63 (all codes); Lower
Extremities: Codes 50-58 (all codes); Multiple Body Parts: Insufficient Info to Properly Identify
- Unclassified (65), Multiple body parts (90), and Body systems and Multiple Body Systems
(91) (Part of Body Injured, Appendix H)
For example, a room cleaner lifts a mattress and feels a strain in her upper arm. This observation
would meet the definition of an MSD injury because it includes: a strain (nature of injury/
subcategory “strain”) + lifting (cause of injury/subcategory “lifting”) + upper arm (part of body
injured/subcategory “Upper Extremities”). A strain caused by lifting and felt in the head would
not be included because the head is not one of the specified part of body injured subcategories.

49
Study Dataset
Setting Parameters
There were 79,052 claims in the Hotel Industry MSD dataset for years 2001-2016 provided by
CA-DWC (Figure 3.2). Based on the results of frequency analyses of the data using SAS®
software, Version 9.4, the data were limited to certain factors. To evaluate gender segregation in
the data, the occupation terms “Housekeeper” and “Room Attendant” accounted for the majority
of claims with occupation terms similar to hotel room cleaning job titles. The proportion of these
two occupations terms that had female claimants were averaged together, resulting in a finding
that 96% of claimants were females. With too few claims with male claimants for a comparison
analysis, the dataset was limited to females. “California” as Employee State accounted for 99.2%
of claims; the data was limited to California residents. The dataset was limited to years 20072016
(n=33,303 claims) as this was when the distribution of claims was the highest (70%).
Validation and Cleaning the Data
Standard methods of data cleaning were performed such as data validation and removing data
that did not meet study inclusion criteria. Timestamps were removed from data fields and
variables were renamed by putting “Clean” in front of the variable name, e.g., “CleanDOB.”
Industry was confirmed using two separate variables from the WCIS dataset: Industry Code and
Class Code (Data Element Nos. 25 and 59, respectively, Vossenas Data Matrix (Appendix E). A
total of 10,303 claims that did not meet the criteria for hotel industry and were not coded as
missing, were excluded (only meets Class Code criteria, not a select Industry Code or select
Missing Industry: n=5,714; only meets Industry Code criteria, not a select Class Code or select

50
Missing Class: n=4,585; neither meets an Industry nor Class Code nor a Missing Industry or
Class Code: n=4). For the remaining 23,070 claims, they were classified as either: 1) confirmed
as hotel industry if both Class and Industry Code variables met the criteria (n=19,652), 2) where
the Class Code criteria was met and the Industry Code was missing (n=2,926); and 3) where the
Industry Code criteria was met and the Class Code was missing (n=492). This recoding permits
the stratification of the data by level of hotel industry verification (one hotel industry code or
two) and the identification of claims where one or both hotel industry codes were missing. In
addition, this recoding allows for performing an analysis to assess the impact of hotel industry
verification level on the accuracy of identifying hotel room cleaners in the occupation data (Aim
1) and/or identifying hotel room cleaner tasks in the task data (Aim 2).
To verify that all claims met the definition of an MSD injury case, frequencies were run on the
Nature of Injury, Cause of Injury and Part of Body Injured variables. All claims met the MSD
injury case criteria. A new variable “Study ID” was created. Study Record numbers, Jurisdiction
Claim Numbers (JCN) and Study ID were checked for duplicates. A file was created matching
the new Study ID with the corresponding Study Record and JCN variables, followed by
removing the latter two variables from the dataset.
De-identification of the Study Dataset: Numeric Data
The claims data provided by CA-DWC were not de-identified. I followed the methods described
in the Safe Harbor §164.514(b)(2) clause of the Health Insurance Portability and Accountability
Act (HIPAA) Privacy Rule and de-identified the study dataset for zipcode, city, date, gender and
age variables and for narrative text data.97 The “Clean” date-related variables were used to

51
generate new date-related study variables: Age Time of Injury, Years Job Tenure Time of Injury,
and Months Job Tenure Time of Injury. Other Clean date-related variables were renamed as the
following new study variables: Year Hire, Year Injury, Year Death, Year Disability Benefit, Year
Last Worked, and Year Return to Work. Subsequently, all original and Clean date-related
variables were removed from the dataset. For claimants with an “Age Time of Injury” response
over 89 years, data were recoded into the response category of “≥90 years.” The variable
“Gender Code” was removed from the dataset as all claimants in the study dataset are female.
“Employee Postal Code” was truncated to the first three digits, creating the new variable
“Zipcode.” The Employee Postal Code and “Employee City” variables were removed.
Study Dataset Samples
The study dataset was subsetted into several sequential data samples as illustrated in Figure 3.2,
to ultimately create two analytic data samples: “Hotel Room Cleaner Occupation MSD” and
“Hotel Room Cleaner Task at Time of Injury.” These two study samples correspond to Aims 1
and 2, respectively. Both aims are concerned with methods to code narrative text data and are the
outcome of the application of list maintenance and natural language processing methods by the
AI experts. After removing non-hotel industry claimants from an earlier iteration, the Female
Hotel Industry MSD Claimant Sample was created for years 2007-2016 (n=23,070 claims).

52
From this data sample, the AI experts applied a “list maintenance” method that resulted in
achieving Aim 1, the identification of the occupation of hotel room cleaner in hotel industry
MSD workers’ compensation claims data. As a result, the “Female Hotel Room Cleaner
Occupation MSD Claims” analytic data sample (n=12,125 claims) was created.
To achieve Aim 2, the identification of the task at time of injury, I subsetted the Aim 1 analytic
data sample to years 2012-2016 (n=6,952 claims), resulting in the “5-Year Female Hotel Room
Cleaner MSD Claims” data sample. The most recent five years of data were selected to reflect
more current changes in hotel accommodations and hotel housekeeping work practices.
De-Identification of the Task Data Sample: Narrative Text Data
Before sending the task data sample to the AI experts, I de-identified the narrative text injury
descriptions that comprise the task data. I followed the Safe Harbor HIPPA guidance about
deidentification of free text data which states “The de-identification standard makes no
distinction between data entered into standardized fields and information entered as free text
(i.e., structured and unstructured text) -- an identifier listed in the Safe Harbor standard must be
removed regardless of its location in a record if it is recognizable as an identifier.”97 Efforts were
made to remove the gender terms “she” and “her,” along with names (worker, supervisor, hotel),
hotel room numbers, dates of injury, adjudication case numbers and diagnoses from the task data
sample. Microsoft Excel ©2016 software features “Filter,” “Find,” “Replace,” and “Sort” were
used to de-identify the data.

53
Application of Natural Language Processing Methods to Task Data Sample
The AI experts applied NLP methods to the task data sample and achieved Aim 2, resulting in the
“Female Hotel Room Cleaner Task at Time of Injury, Years 2012-2016” analytic data sample.
After further refining the parameters of the coded task data sample (restrict claims to
Hotel Room Cleaner =1 “Yes,” n = 6,952; remove the “Unknowns,” n = 3,013; remove claims
with a “<70% confidence level,” n = 1,310), the sample size is reduced to 2,629 claims (includes
1 missing injury incident data [task]). As a result of achieving Aims 1 and 2, the analytic data
samples for Aims 3A and 3B are created.
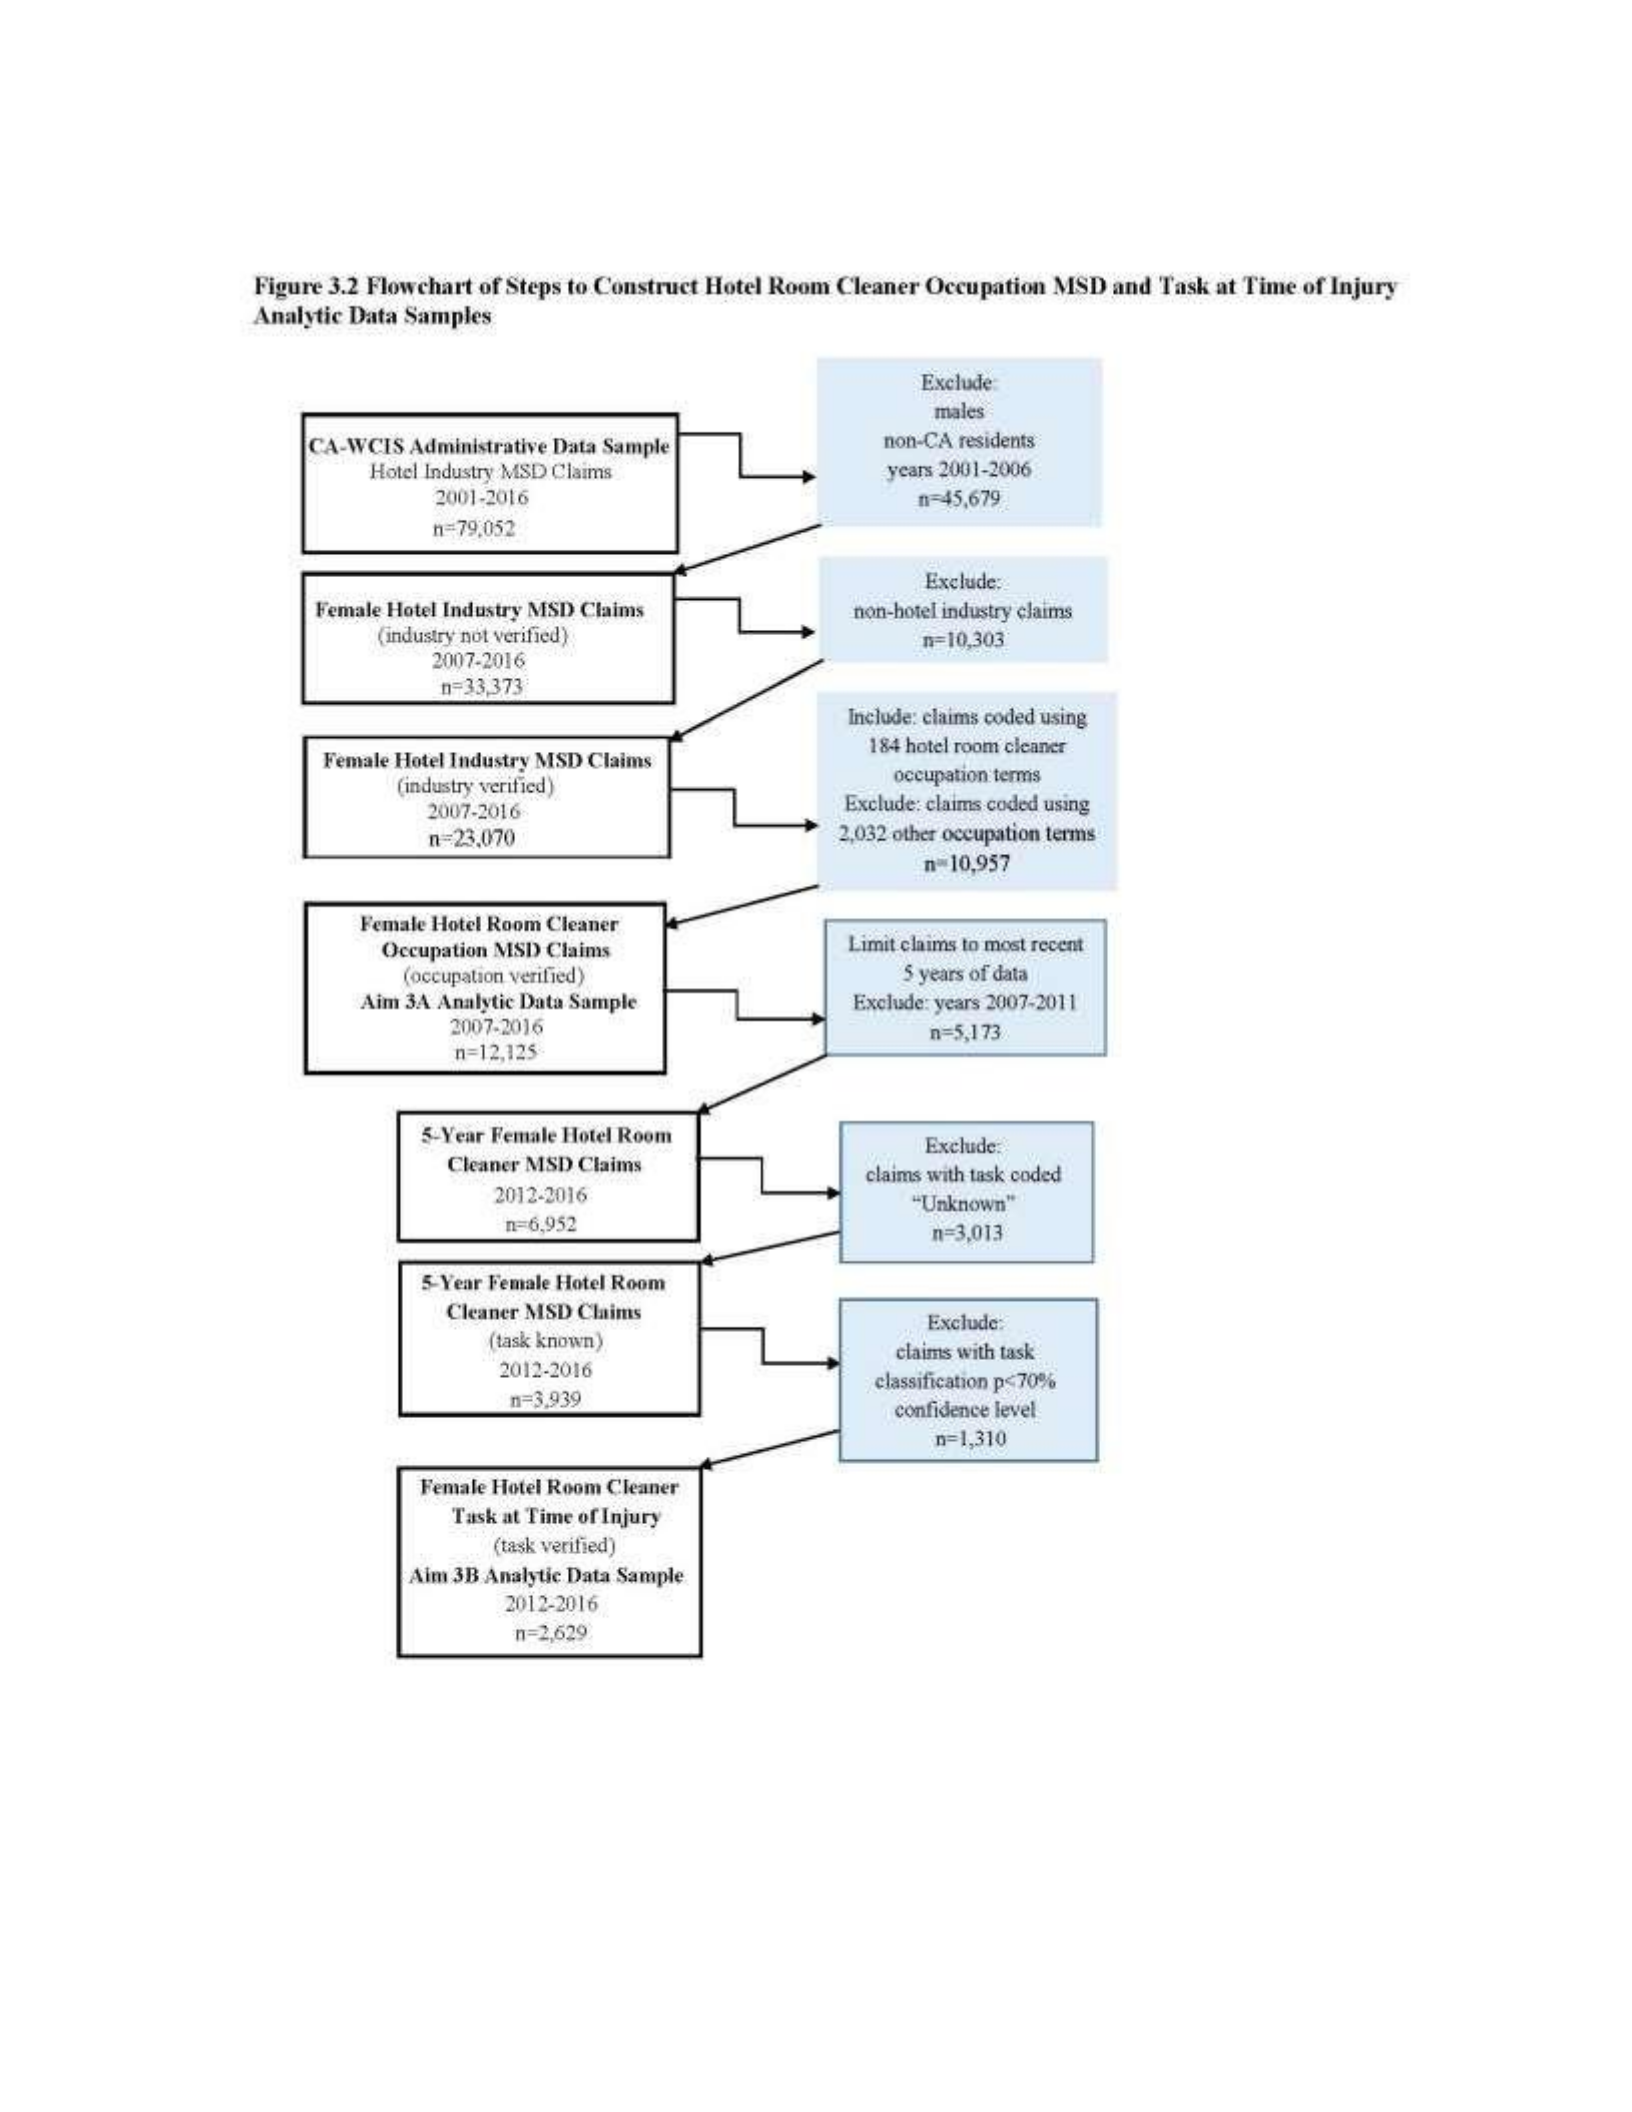
Figure
3.2
Flowchart
of
Steps
to
Construct
Hotel
Room
Cleaner Occupation
MSD
and Task
at
Time
of Injury
Analytic
Data
Samples
Exclude
males
JCA-WCIS
Administrative
Data
Sample|
Bah
neces
Hotel
Industry
MSD
Cums
years
2001-2006
2001-2016
945679
n=79.052
Exclude:
Female
Hotel
Industry
MSD
Claims
‘non-botel
industry
claims
‘Gndustry
not
verified)
910303,
2007-2016
33373
enero
(industry
verified)
eaten
ao
ae
ae
——
ne
10,987
See
aac
Res
an
Ss
sa
ee,
ae
ahi
wee
claims
with
task
coded
a
ed
3.013
=e
ae
=
Sire
Ld
cit
aoe
oe
os
—
ESSE
eae
Aim
3B
Analytic
Data
Sample
54

55
Description of Artificial Intelligence Methods for Classifying Narrative Text Data
Wiseyak Inc. is a healthcare technology firm located in Bellevue, WA and Kathmandu, Nepal
that uses artificial intelligence (AI) and natural language processing)-based solutions for
healthcare data challenges. Wiseyak Inc. was hired to create AI solutions using NLP techniques
to classify and code narrative text fields of thousands of claims by occupation and by task. I
worked with experts from Wiseyak starting in 2019, some of whom who were based in
Kathmandu, Nepal. We collaborated via email, Skype and Google Meet. Wiseyak Inc. is referred
to as the “AI team” throughout my dissertation.
The AI team applied two categories of methods to the narrative text variables (Figure 3.3) that
originated from the CA-WCIS dataset: “Occupation_Descr” and “Accident Description/Cause.”
These methods transform narrative text data into quantitative data, adding three new study
variables suitable for data analysis: “Hotel Room Cleaner Occupation” and “Hotel Room Cleaner
Job Title” (Aim 1, both variables) and “Task at Time of Injury” (Aim 2).
Aim 1: Application of List Maintenance Method to Occupation Description Narrative Text Data
The AI team used a “list maintenance” method to identify occupation terms from the occupation
description narrative text data found in the “Occupation_Desc” variable. This method classified
the occupation terms, using the “Occupation Terms List” and corresponding response codes for
the newly created “Hotel Room Cleaner Occupation” variable (answering the question, Is the
claimant a Hotel Room Cleaner?). Although the AI team applied the list maintenance method, it
is not considered an “AI” or “NLP” method. The same method was applied to classify the

56
occupation terms by a second list, the “Hotel Room Cleaner Job Title List” and corresponding
response codes for the newly created “Hotel Room Cleaner Job Title” variable (claimant’s
category of hotel room cleaning job title, e.g., maid, room attendant, housekeeper). The
occupation terms ranged from one to five words each.
I provided the AI team the lists of occupation terms and response codes for the two occupation
variables. According to Wiseyak, a fixed number of unique data with numerous misspellings of
the occupation terms made using Language Processing methods impractical.† The occupation
description terms were usually limited to one to three terms. Examples of spelling variations
and/or errors in the occupation terms include, for example: Room Attendant, Room Attendent,
Room Attendand, Room Attendance, and Rm Attendant. The above details and more are
provided from the AI team in a report by Shankar Poudel included in Appendix I.
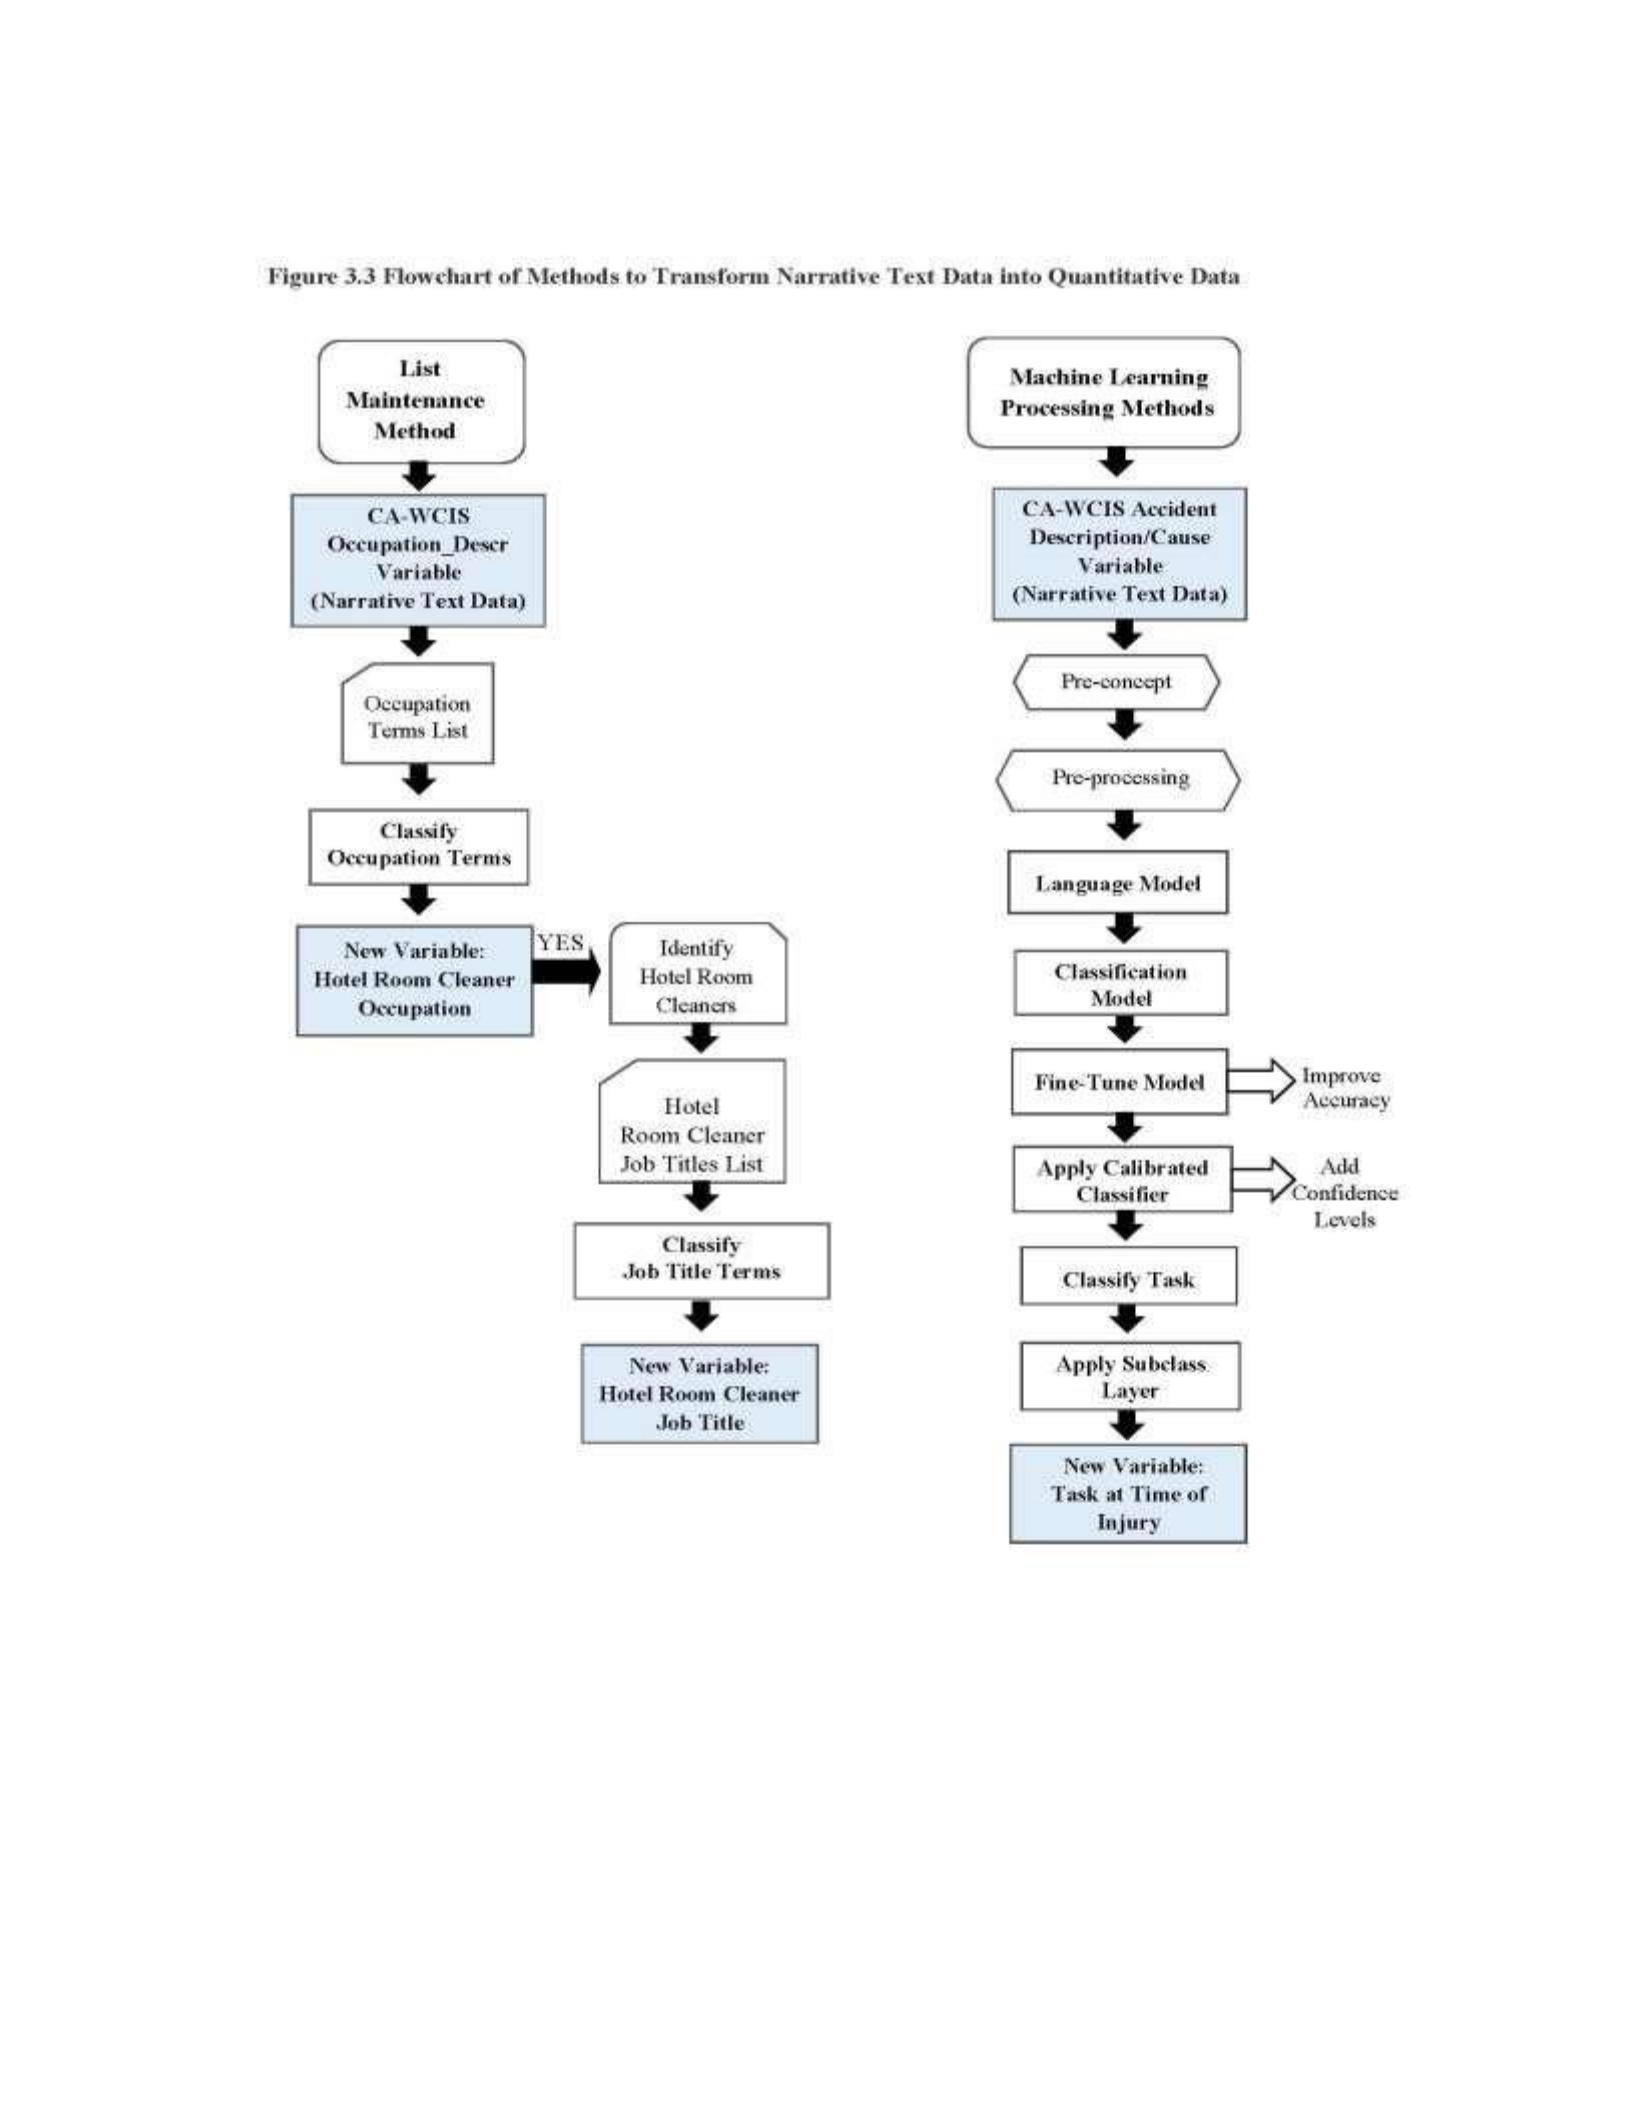
Figure
3.3
Flowchart of
Methods
to
Transform
Narrative
Text
Data
into
Quantitative
Data
Machine
Learning
Processing
Methods
Tana
CAC
Sec
it
seule
Toate
ona
oer
Testa
oer
ot
(reomot_)
cesisn
coi
car
eva
Fr
7
Canpog
Noe
—s
deity
*
tithe
we
|
acon
eae
conten
See
oe
Fine-Tune
Model
ee,
Hotel
oa
Room
Cleanse
¥
Sob
Tales
st
TppiyCatricd
Aa
Citar
once
Tee
Classify
¥
soo‘
Terms
clase
in
‘New
Variable:
“Task
at
Time
of
Injury
57
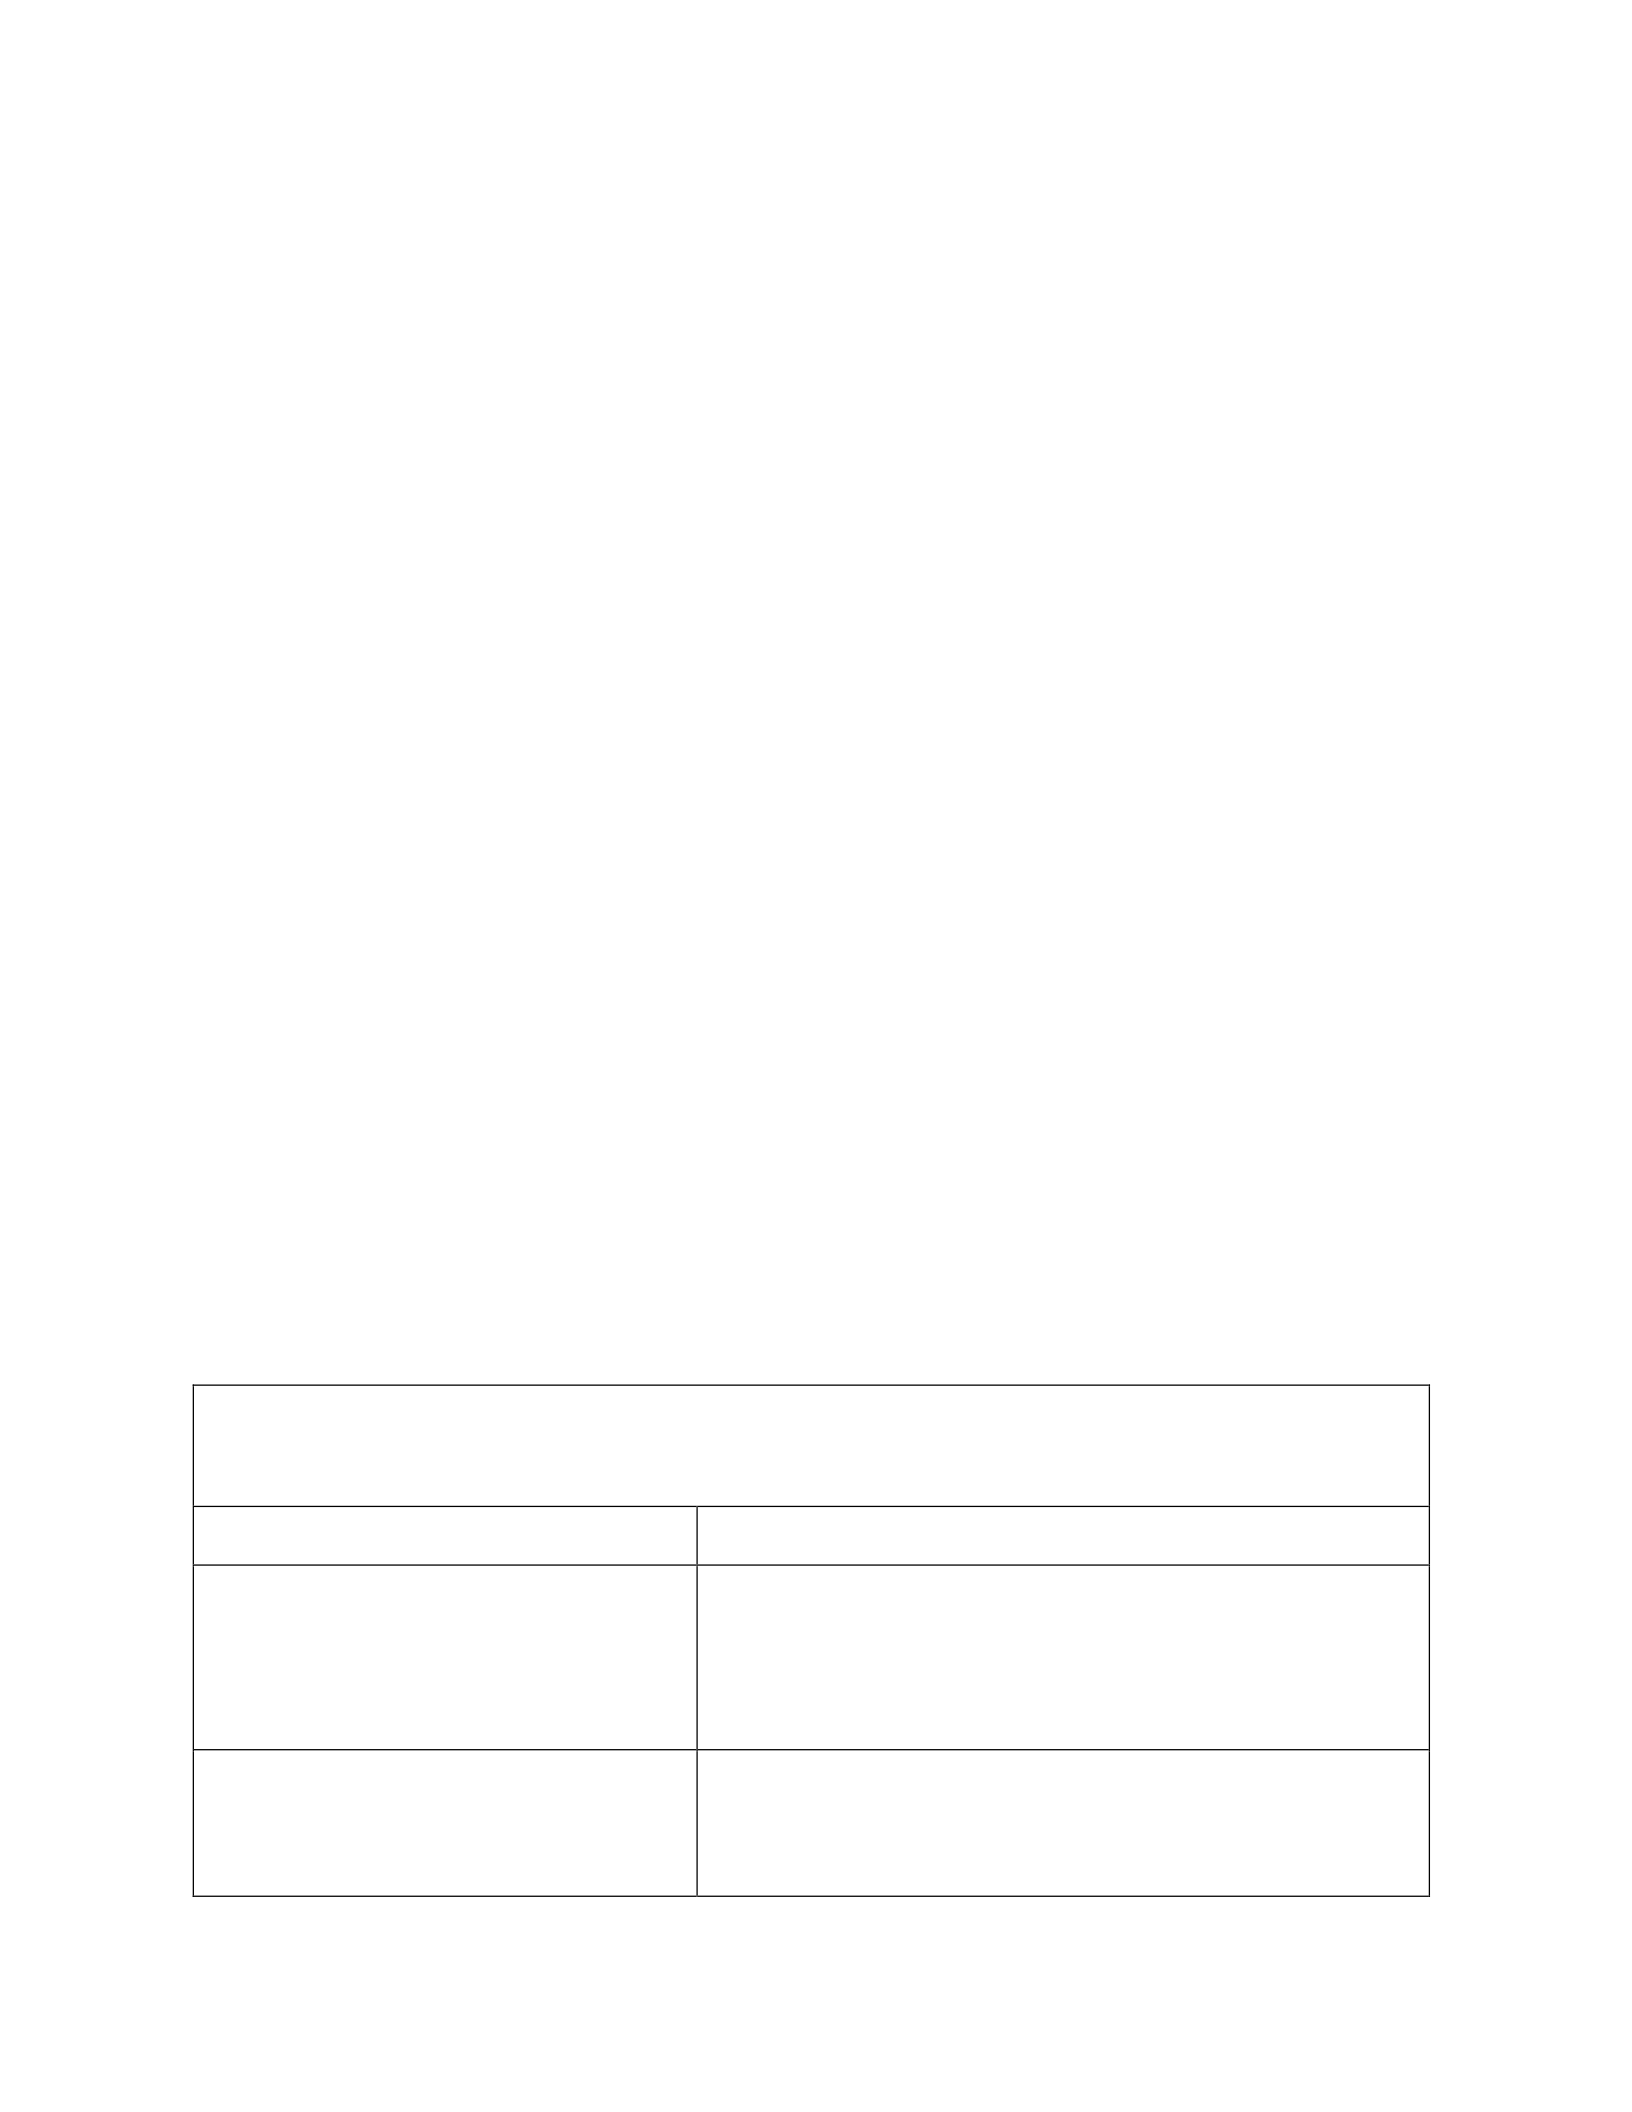
58
Aim 2: Application of Machine Learning Processing Methods to Injury Description Narrative
Text Data
Unlike the occupation description narrative text data, the injury description narrative text data
consist of several words or a couple of sentences, making it possible to use Machine Learning
Processing (MLP) methods to classify this data. Several MLP methods were applied, each with
its own distinctive utility and role (Table 3.1). The objective of the AI methods is to create a
language model that generates a key vocabulary of terms from the injury descriptions. Then a
classification model uses this vocabulary to classify the injury description narrative text data into
coded data. The utility of the MLP methods are discussed in the literature, in particular, in
articles recommended by the AI team about the use of Support Vector Machines (SVMs) for text
classification and Term Frequency-Inverse Document Frequency (TF-ID) to assess the
importance of key words in the data.98-100 More details are provided from the AI team in a report
included in Appendix I.
Table 3.1 Application of Machine Learning Processing Methods to Classify Injury
Description Narrative Text Data (Aim 2), excerpts from Appendix I.
Application of Machine Learning Processing Methods:
Classification of Injury Description Narrative Text Data for
Task at Time of Injury Variable
Methods
Key Features
Pre-concept
The concept at the onset of the classification process to
classify the data into 9 classes (codes). Sub-classes, e.g.,
making a sofa bed comes under bedmaking task (class “2”),
are classified later in “layering” phase post-application of
the classification model.
Pre-processing
Prepare the text to maximize its significance for the
vocabulary that generates the language model. Remove
“stop” words such as “the” and “a” and apply “stemming”
to reduce words like “pushing” and “pushes” to “push.”
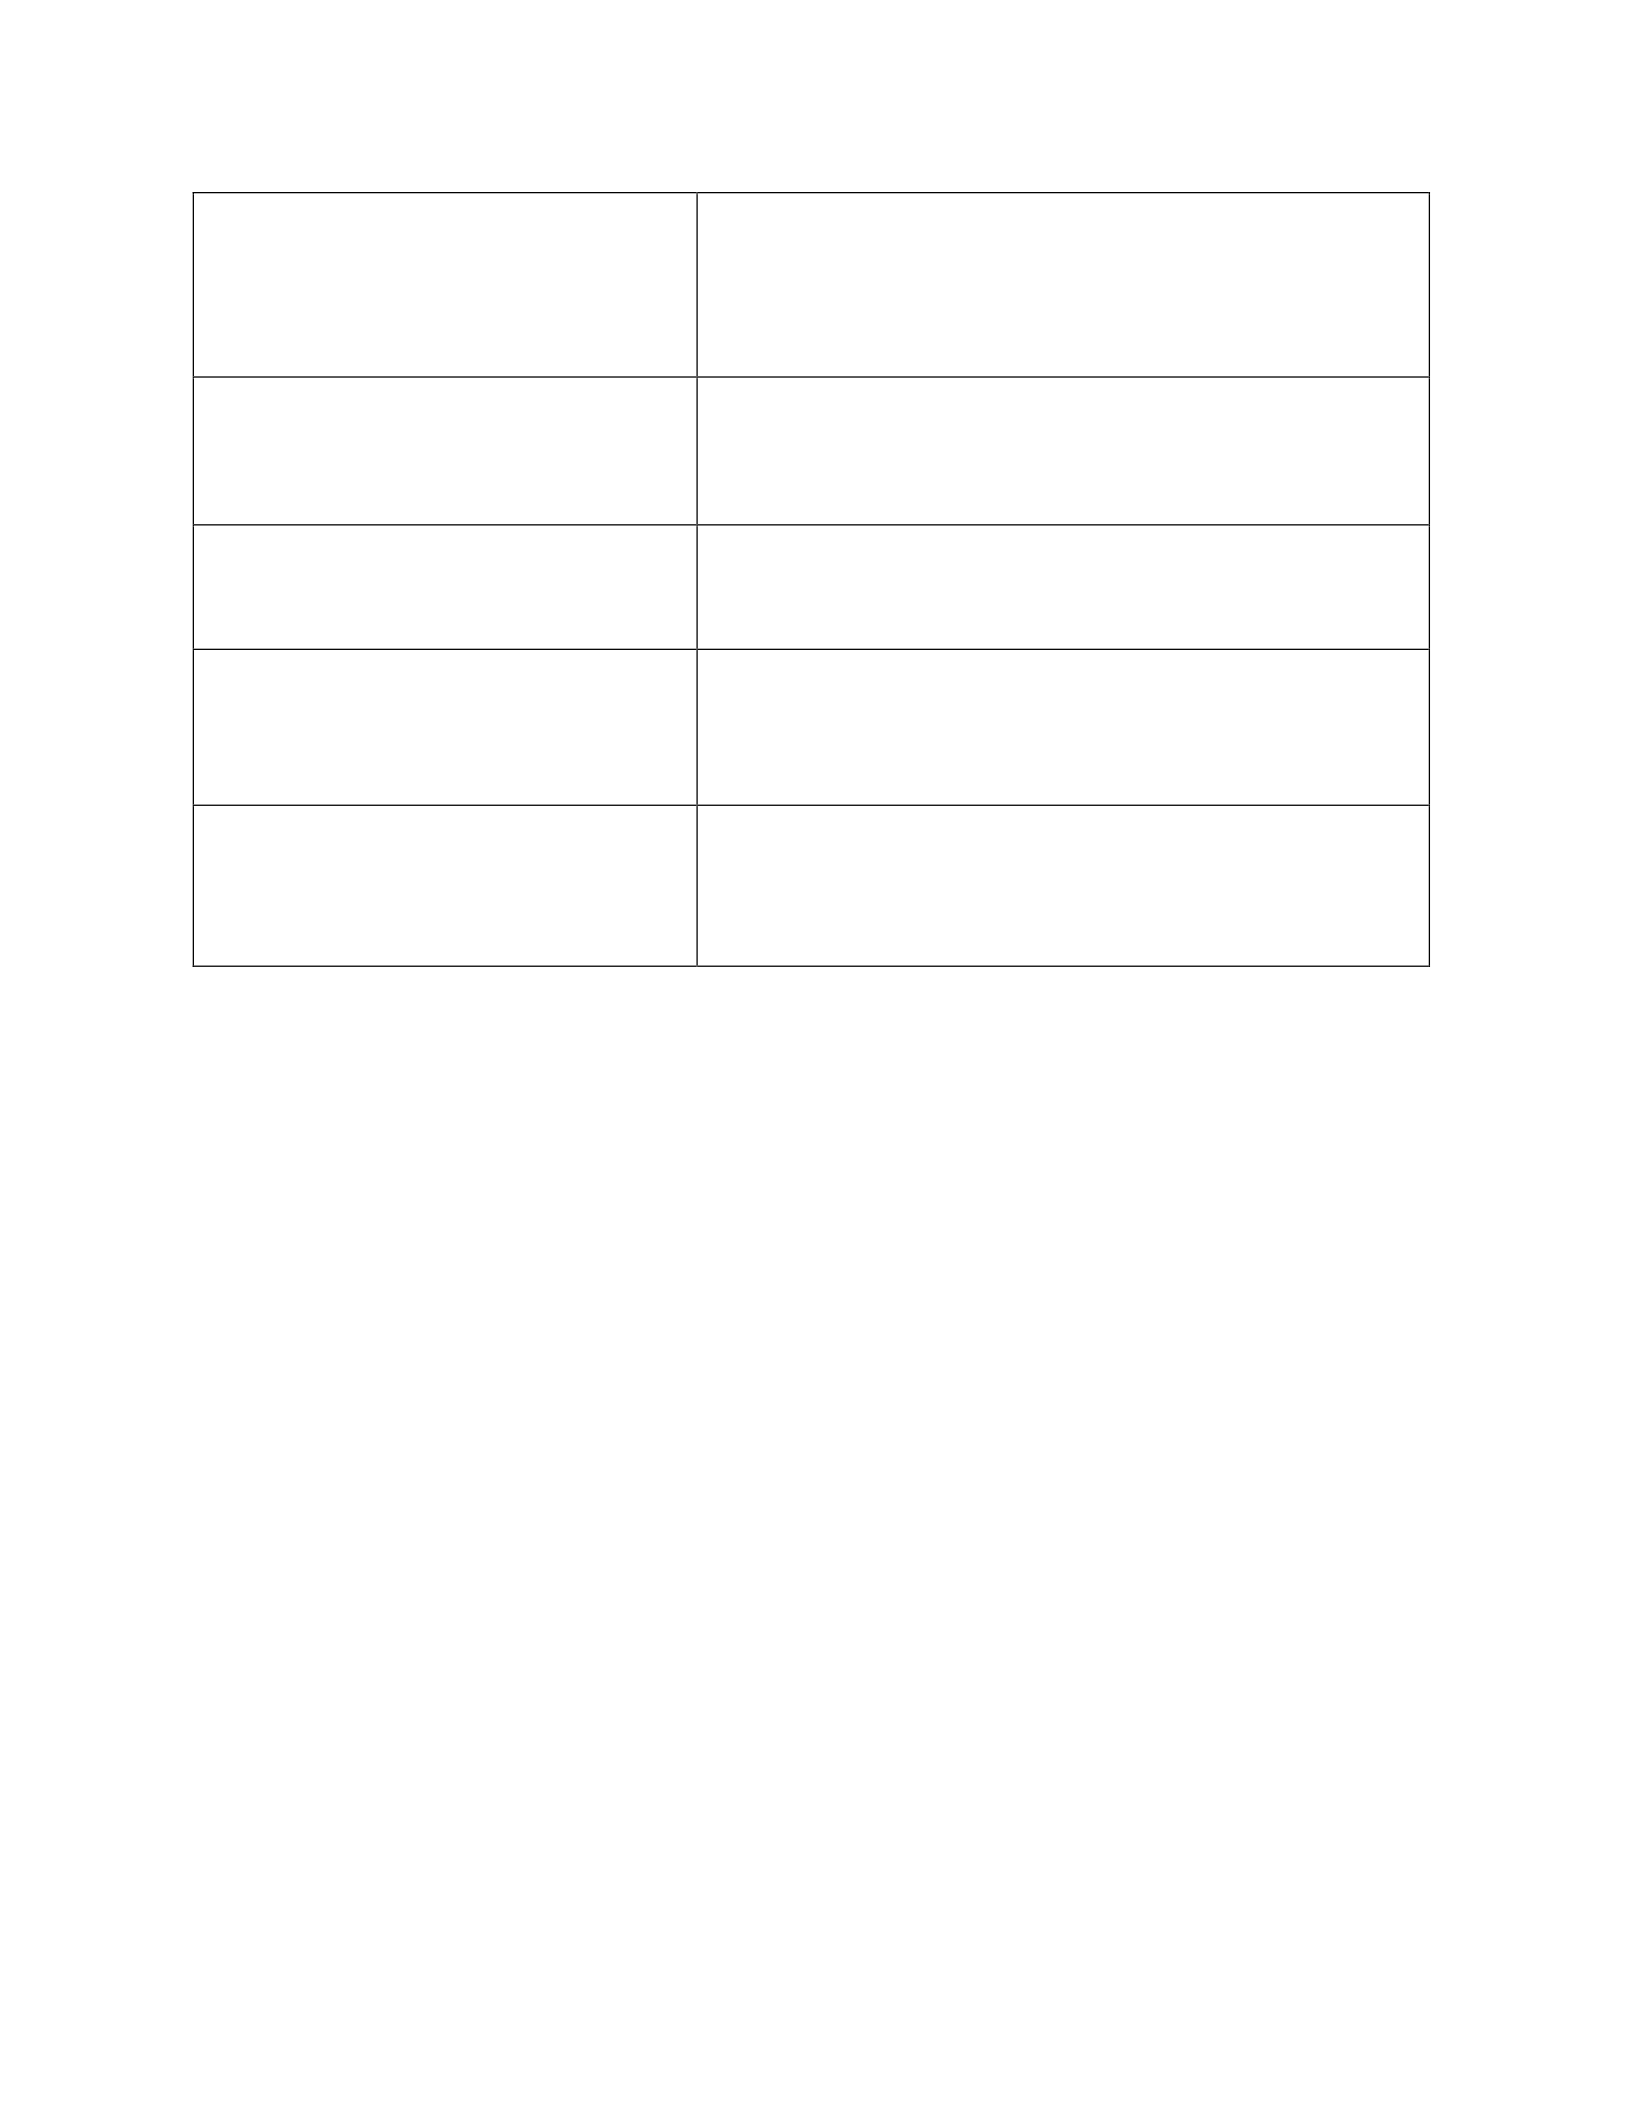
59
Language Model
“Term Frequency-Inverse Document Frequency” vectorizer
is used to calculate the importance of each word for
classification in the training dataset. Then “high
importance” words were filtered to create vocabulary that is
used to classify each injury description in the model.
Classification Model
The one vs. rest multiclass linear SVM algorithm is used to
create a ML model as it produced results similar to those
generated by complex algorithms, with the added
convenience of being able to use “Calibrated Classifier.”†
Fine-tuning Classification Model for
Improved Accuracy
Methods applied to enhance accuracy result in small
improvements: 1) regularization (c-parameter), 2) kernel,
3) gamma parameter, 4) margin.
Calibrated Classifier
Application of “Calibrated Classifier” produces a
confidence level (probability) for each class, namely that
the model accurately predicted which class the injury
description belongs to.
Application of Subclass Layers
Sub-classes are created now that the data has Class and
Confidence Levels, e.g., making a sofa bed changes from
class “2, Bedmaking” to subclass “21, Making a Sofa Bed”
The sub-class data are now added to rest of the class data.
Study Variables
Hotel Room Cleaner Occupation (New Variable)
Hotel Room Cleaner Occupation is defined as whether or not the claimant is a Hotel Room
Cleaner and is a new variable with the following values: 1) yes; 2) no; 3) maybe; 4) questions;
5) misclassified; 8) missing; 9) unknown.
Hotel Room Cleaner Job Title (New Variable)
Hotel Room Cleaner Job Title is defined as the claimant’s job title within the occupation of Hotel
Room Cleaner and is a new variable with the following values: 1) housekeeper; 2) room
attendant; 3) room cleaner; 4) maid; 5) houseperson; 6) not applicable.

60
AgeTRUE Time of Injury (New Variable)
AgeTRUE Time of Injury is defined as the claimant’s age at time of injury incident. This is a new
variable created using the data from the Age Time of Injury variable and removing claimants
aged less than 18 years. The Age Time of Injury variable is a new variable created during the de-
identification of data phase. It was created using the SAS INTCK procedure that computed the
time difference in years between Employee Date of Birth and Date of Injury.
Age Group (New Variable)
Age Group is defined as the age group interval in years to which the claimant belongs and is a
new variable with the following values:
18-24
25-34
35-44
45-54
55-64
65-69
70-74
75+
YearsTRUE Job Tenure (New Variable)
YearsTRUE Job Tenure is defined as number of years of service with employer at time of injury
incident. YearsTRUE Job Tenure is a new variable created using data from the

61
Years_JobTenureTimeInj variable and moving negative and extreme values to missing. The
Years_JobTenureTimeInj variable is a new variable created during the de-identification of data
phase. It was created using the SAS INTCK procedure that computed the time difference in
years between Date of Hire and Date of Injury.
MonthsTRUE Job Tenure (New Variable)
MonthsTRUE Job Tenure is defined as number of months of service with employer at time of
injury incident. MonthsTRUE Job Tenure is a new variable created using data from the
Months_JobTenureTimeInj variable and moving negative and extreme values to missing. The
Months_JobTenureTimeInj variable is a new variable created during the de-identification of data
phase. It was created using the SAS INTCK procedure that computed the time difference in
months between Date of Hire and Date of Injury.
Tenure Group (New Variable)
Tenure Group is defined as the tenure group interval to which the claimant belongs and is a new
variable created with data from the MonthsTRUE Job Tenure variable with the following values:
≤6 months
6 months-1 year
1-2 years
2-5 years
5-10 years
10-20 years
20+ years

62
Task at Time of Injury (New Variable)
The variable “Task at Time of Injury” identifies the specific job task the hotel room cleaner was
performing when injured. This new variable is based on narrative text data from the “Accident
Description/Cause” variable coded into seven task categories from the Cal/OSHA Title 8. Hotel
Housekeeping Musculoskeletal Prevention standard, Section (b). Definitions: ‘“Housekeeping
tasks” means tasks related to cleaning and maintaining sleeping room accommodations including
bedrooms, bathrooms, kitchens, living rooms, and balconies. Housekeeping tasks include, but are
not limited to, the following: (1) sweeping, dusting, scrubbing, mopping and polishing of floors,
tubs, showers, sinks, mirrors, walls, fixtures, and other surfaces; (2) making beds; (3)
vacuuming; (4) loading, unloading, pushing, and pulling linen carts; (5) removing and supplying
linen and other supplies in the rooms; (6) collecting and disposing of trash; and (7) moving
furniture.”1 These housekeeping task categories were used verbatim as “Task Category” codes.
Three subclassifications were created for emerging hazards for Task Category 2 - Bedmaking:
“21” rollaway; “22” sofa bed; and “23” Murphy bed. Additional codes were created: “88”
missing; “9” unknown for data where task was not determined; “91” cleaning rooms (generic use
of the term “cleaning”); “92” non-hotel room cleaner task; “93” other hotel room cleaning task;
“94” walking; “97” regular duties; “98” pain/injury/worker motion/diagnosis; “99” not
applicable. For data analysis, three task category codes can be collapsed into one “9” unknown
category: “91” cleaning rooms (generic use of the term “cleaning”); “97” regular duties; and
“98” pain/injury/ worker motion/diagnosis. Subject matter experts1 recommended adding
“unknown” as a response category since previous research coded task as unknown for 33% of
WCIS cases studied.47 With “Unknown” as a response category, an analysis of differences
between claims with and without an identified task at time of injury is possible.

63
Nature of Injury (WCIS Data Element Number (DN) 35)
Nature of injury codes for “specific injury” or “cumulative injury or disease” from the California
WCIS that relate to musculoskeletal disorders were used in descriptive analyses to characterize
the MSD injuries by nature of injury. These subcategories were used by earlier researchers to
identify MSDs in hotel housekeepers and healthcare workers.11 These subcategories include
Dislocation (16), Hernia (34), Inflammation (37), Sprain (49), Strain (52), All Other Specific
Injuries, NOC (59), All Other Occupational Disease Injury, NOC (71), VDT-related disease (76),
Carpal Tunnel Syndrome (78), and Multiple Injuries Including Both Physical and Psychological
(91). All other nature of injury codes were excluded.
Cause of Injury (DN 37)
Cause of injury codes from the California WCIS subcategories that relate to musculoskeletal
disorders were used in descriptive analyses to characterize the MSD injuries by cause of injury.
These subcategories and codes were used by preceding researchers as stated earlier to identify
MSDs in hotel housekeepers and healthcare workers.11 These subcategories include Strain or
Injury by: Codes 53-61, 97; Striking Against or Stepping Down: Sanding, Scraping, Cleaning
Operation (67); Rubbed or Abraded: Repetitive Motion (94), Rubbed or Abraded, NOC (95); and
Miscellaneous Causes: Cumulative, NOC (98). All other cause of injury codes were excluded.
Cause of Injury Category (New Variable)

64
Cause of Injury Category is defined as the category of injury causes to which the claimant’s
injury was attributed. The Cause of Injury Category is a new variable based on the categories
from the California WICO injury codes found in Appendix H, with the following values: Strain
or Injury By; Striking Against or Stepping Down; Rubbed or Abraded; and Miscellaneous
Causes.
Part of Body Injured (DN 36)
Part of Body (DN 36) codes from the California WCIS subcategories were used in descriptive
analyses to characterize the MSD injuries by the part of body injured. These subcategories and
codes were used by preceding researchers as stated earlier to identify MSDs in hotel
housekeepers and healthcare workers.11 These subcategories include Neck: Codes 20-26; Trunk:
Codes 40-49, 60-63; Upper Extremities: Codes 30-39; Lower Extremities: Codes 50-58; and
Multiple Body Parts: Insufficient Info to Properly Identify-Unclassified (65), Multiple Body
Parts (90), Body Systems and Multiple Body Systems (91). All other part of body codes were
excluded. The Part of Body Variable is comprised of Part of Body values from the included
subcategories.
Part of Body Category (New Variable)
Part of Body Category is defined as the category to which the claimant’s injured part of body
belongs. The Part of Body Category is a new variable based on the categories from the California
WICO injury codes found in Appendix H, with the following values: Neck; Trunk; Upper
Extremities; Lower Extremities; and Multiple Body Parts.

65
Data Analysis
Application of Methods by the AI Team to Transform Narrative Text Data into Quantitative Data
Aim 1: Identification of Hotel Room Cleaner Occupation
I provided the AI team with an excel spreadsheet containing 23,070 hotel industry MSD claimant
records for years 2007-2016 (all females), a list of codes for response values for the research
question, “Is this a Hotel Room Cleaner?” and a list of codes to classify the hotel room cleaner’s
job title, e.g., housekeeper, maid, etc. The AI team used a list maintenance method described
earlier in this chapter to classify the records by both lists, thereby creating two new variables:
“Hotel Room Cleaner Occupation” and “Hotel Room Cleaner Job Title.” I received a csv file
from the AI team with the same 23,070 records coded for these two new variables.
Aim 2: Identification of Task at Time of Injury
I provided the AI team with an excel spreadsheet containing 8,442 records for years 2012-2016
(all females) that was comprised of records where the Hotel Room Cleaner Occupation was
coded as 1) Yes, 3) Maybe and 4) Questions and a list of codes for response values for the
research question, “What was the Task at Time of Injury?”. The AI team applied Machine
Learning Processing methods described earlier in this chapter (Table 3.1) to classify the injury
description narrative text data. This transformed the narrative text data into quantitative data,

66
thereby creating the new variable: “Task at Time of Injury.” I received a csv file from the AI
team with the 2012-2016 data coded for this new variable.
Quality Control Sampling of Narrative Text Data Classified into Task Categories
Before analyzing the Aim 3B analytic data sample, I performed quality control checks on the
coded responses for a sample of each of the seven task categories, i.e., Task Category 1:
Cleaning, Task Category 2: Bedmaking, Task Category: 3 Vacuuming, etc. After performing a
quality control check on a 20% sample of Task 1: Cleaning with 1,235 claims and at the
recommendation of doctoral faculty, I decided to create an algorithm a priori to decide on the
sample size for quality control checks based on the number of claims per task category. Below is
the algorithm I devised apriori:
Use a 15% sample for quality control checks for tasks with >100<200 claims;
Use a 10% sample for quality control checks for tasks with >200 claims; and
Use a 20% sample for quality control checks for tasks with <100 claims.
After all task categories were sampled, then the total number of records sampled was used to
enumerate an averaged percent of records sampled for the task dataset overall.
I evaluated each task category on key indicators of accuracy of the classification of task data that
I devised: % claims hotel room cleaner (HRC)-related, % claims classified correct and % claims
with ≥70% confidence level. The AI team recommended ≥70% confidence level as a standard
cut-off point for accuracy of the data, as this is considered a best practice in the literature
(Marucci-Wellman et al., 2017). Having observed accurate coding in the data at levels <70%, I

67
also evaluated the accuracy of each sample by three coding confidence levels: ≥70%, 60-69%
and <60%. This allowed me to determine if I should consider adjusting the cut-off point for
including task data on a task category basis, based on that task category’s specific results for
accuracy by confidence level category, e.g., task x cut-off is 60-69% because 100% of claims in
the sample at this confidence level were coded correctly.
In addition to the above indicators, I calculated two estimates for each task category: estimated N
of claims with ≥70% confidence level and estimated N of claims with correct task coding at the
≥70% confidence level. The first estimate is calculated by multiplying the percentage classified
correctly by the total number of claims for a specific task category. Using the ≥70% confidence
level as a cut-off point, this first estimate would equal the number of claims in the task dataset
for each task category that would be included for Aim 3B data analysis. The second estimate is
calculated by multiplying the total number of claims from the first estimate by the percentage of
claims with a ≥70% confidence level that are coded correctly. For example, suppose there are
1,000 claims for task x with 80% of those claims are in the ≥70% confidence level category and
the accuracy rate for the ≥70% confidence level category is 90%. The first N would yield 800
claims estimated to be added to the data analysis for task x using the ≥70% confidence level
category as the cut-off inclusion criteria. Of those 800 claims, the second N would yield 720
claims estimated to be correct. After both sets of estimates were calculated for all tasks, the total
number of records estimated to be correctly classified in the ≥70% confidence level category was
used to enumerate an averaged accuracy rate for estimated records overall for the task dataset.

68
Descriptive Analyses: Demographics, Injuries and Task Analysis (Aims 3A and 3B)
Aim 3: Descriptive Analyses: Study Population, Injury Characteristics and Task at Time of Injury
To perform basic descriptive statistical analyses to characterize MSD injuries in hotel room
cleaners by age at time of injury, age group, years job tenure, months job tenure, tenure group,
nature of injury (e.g., sprain or tears), cause of injury category (e.g., Strain or Injury By), cause
of injury (e.g., twisting), part of body category (e.g., Upper Extremities, Trunk), part of body
(e.g., upper arm, low back area), and task at time of injury.
Aim 3A: Descriptive Analyses: Study Population and Injury Characteristics, Years 2007-2016
Descriptive statistical analyses were performed to characterize the hotel room cleaner study
population for years 2007-2016. The study population was limited to female claimants as
explained earlier in this chapter with a response of Yes=1 for the hotel room cleaner occupation
variable. The total number of hotel room cleaner MSD injury claimants (12,125) was identified
with a breakdown by Hotel Room Cleaner Job Title.
Pearson correlation coefficients with P values and number of observations were generated for
AgeTRUE Time Injury with MonthsTRUE and YearsTRUE Job Tenure variables. As part of
performing the SAS Correlation Procedure, the mean, standard deviation and minimum and
maximum values were generated for these three variables. With minimum and maximum values
identified for AgeTRUE Time Injury (18-90 years), it was possible to calculate the maximum
possible job tenure by years (72 years) and by months (864). All other values, including negative

69
values and extreme values, were classified as missing for the tenure variables. For the maximum
age value, ≥90 years was determined to be the maximum age according to requirements of the
Safe Harbor §164.514(b)(2) clause of the Health Insurance Portability and Accountability Act
(HIPAA) Privacy Rule.97 All age values ≥90 years were classified as “90” years as part of the
de-identification of the dataset phase described earlier in this chapter. The SAS Frequency
Procedure was used to analyze the distribution of female hotel room cleaner MSD claimants by
age group and tenure group. Number of observations and percentages were reported.
Descriptive statistical analyses were performed using the SAS Frequency Procedure to
characterize MSD injuries in hotel room cleaners by injury variables (nature of injury, cause of
injury category, cause of injury, part of body category, part of body). All injury variables are
categorical variables. Subcategories of these three variables were determined by the distribution
of the study data. Number of observations and percentages were reported.
Aim 3B: Descriptive Analyses: Task at Time of Injury, Years 2012-2016
Descriptive statistical analyses were performed using the SAS Frequency Procedure to
characterize MSD injuries in hotel room cleaners using injury variables stratified by seven task at
time of injury categories and counts of claims by task at time of injury is reported. The seven
task categories are described in the Variable Definition for the ‘Task at Time of Injury’ variable
an. Injury variables include: cause of injury, e.g., lifting, carrying, twisting, etc.; nature of injury,
e.g., strain, sprain, contusion; and part of body injured. Subcategories of these three variables
were determined by the distribution of the study data for each task category. Injury variables

70
were sorted by seven task categories and percentages of injury are reported, along with sample
size for each task.
Section 4: Results
Part 1: Transformation of Narrative Text Data into Quantitative Data
This section describes the steps taken to transform narrative text data for occupation and task into
quantitative data, focusing on the creation of new variables and response codes; the subsetting of
claims data into sequential data samples based on the responses and corresponding decisions
made based on the data; and quality control checks on each new data sample and key variables.
The utility of the variables for this study and their potential for future research will be discussed
in Section 5, Conclusions and Discussion.
Aim 1. Identification of Hotel Room Cleaner Occupation
Creation of the “Female Hotel Industry MSD Claims” Data Sample
To achieve Aim 1, the identification of the occupation of hotel room cleaner in hotel industry
MSD workers’ compensation claims data, the Female Hotel Industry MSD Claims data sample
was created, following the methods detailed in Section 3 Methods. As a result, there are 23,070
hotel industry MSD claims for all occupations for female claimants in the dataset for study years
2007-2016.

71
Creation of the “Hotel Room Cleaner Occupation” Variable and Response Codes
A new variable “Hotel Room Cleaner Occupation” was created and identifies whether the
claimant’s occupation is related to the job of hotel room cleaning based on the occupation listed
in the narrative text field from the Occupation_Desc variable. This variable determines whether
or not a claim is added to the “Female Hotel Room Cleaner Occupation MSD Claim” data
sample and whether or not it is counted as an MSD injury having occurred to a female hotel
room cleaner. There were 2,216 unique occupation terms identified for all claims in the dataset.
I selected job titles from the definition of “Housekeeper” from the Cal/OSHA Title 8. Hotel
Housekeeping Musculoskeletal Prevention standard to use to code all claims: “Housekeeper”
means an employee who performs housekeeping tasks and may include employees referred to as
housekeepers, guest room attendants, room cleaners, maids, and housepersons” (emphasis
added).1 These job titles were used to determine which of the 2,216 occupation terms in the
dataset pertained to the occupation of hotel room cleaner. I identified a total of 184 unique
occupation terms that included one of the above five housekeeper job titles. There were several
iterations of each of the five job titles due to spelling errors, and non-standard nomenclature, e.g.,
multiple abbreviations for the same term.
All claims were coded to answer the research question “Is this occupation term a hotel room
cleaner?” The response categories are 1) “hotel room cleaner” – observations that meet the hotel
room cleaner definition; 2) “non-hotel room cleaner” – observations that do not meet the “hotel
room cleaner” definition; 3) “possible-hotel room cleaner” – observations that may meet the

72
“hotel room cleaner” definition, referred to as “Maybe” category; 4) “questionable-hotel room
cleaner” - observations that are uncertain if they meet “hotel room cleaner” definition, referred to
as “Question” category; 5) misclassified text; 8) missing and 9) unknown.
I developed an algorithm to aid in the decision-making about coding occupation terms that were
unclear if the claim was a hotel room cleaner, resulting in the “Maybe” and “Question”
categories. To illustrate the coding algorithm, for each claim, the occupation term was compared
to the five occupation categories and coded following these guidelines: exact match, code “yes,”
(1); no match, code “no,” (2); includes one of the five occupation categories plus another term,
code “maybe,” (3); and includes one of the five occupation categories plus another term that is
not clear if it is related to hotel room cleaning, code “questions,” (4). For example, the
occupation term “housekeeper” is an exact match, code yes; “housekeeper support,” code as
maybe; “housekeeper sup,” code as questions because it could be housekeeper support or
housekeeper supervisor; “housekeeper supervisor,” code as no; “worker,” code as unknown (9),
and “9050 HOTELS - ALL EMPLOYEES,” code as misclassified text (5). Empty fields were
coded as “Missing,” (8). Where questions arose on certain occupation terms such as “Executive
Housekeeper” or “Turndown Attendant,” other sources of information were consulted such as job
descriptions in employment websites, e.g., “Indeed,” job classifications from union contracts
with hotel employers, O*Net Summary Reports for Maids and Housekeeping Cleaners
(372012.00),21 scientific literature, and government research studies.

73
Creation of the “Hotel Room Cleaner Job Title” Variable and Response Codes
Another new variable “Hotel Room Cleaner Job Title” was created using the same five variable
response codes described above: “housekeepers, guest room attendants, room cleaners, maids,
and housepersons.”1 This variable answers the study research question, “What is the job title of
the injured hotel room cleaner?” This variable determined whether or not the claimant was coded
as working in a hotel room cleaner job title, allowing for future data analysis by job title.
Based on the job title term, the claim was then coded by hotel room cleaner job title. A “Not
Applicable,” 6 response category was created for all non-hotel room cleaner responses. In
addition, two subclassifications: “Not Applicable, Maybe,” (63) and “Not Applicable, Question,”
(64) were created to correspond to the response codes “Maybe,” (3) and “Question,” (4) for the
Hotel Room Cleaner Occupation. This makes it possible to perform an analysis in the future to
identify how similar the injury and task experience is for claims with Maybe and Question codes
compared to claims identified as hotel room cleaners. Then, depending on the findings of such an
analysis, this provides the opportunity to recommend consideration of Maybe and Question job
titles as occupation terms with hotel room cleaning-related MSDs.
Testing AI Team’s Methods on Hotel Room Cleaner Occupation and Job Title Response Codes
The AI team requested training data – examples of occupation terms from the narrative text
“Occupation_Desc” variable. I provided them a “training” subsample of 1,000 claims consisting
of 100 randomly selected claims for each of the ten study years. This training subsample was
shared with the AI team to filter and code the claims by hotel room cleaner occupation and job
title category, the two new variables related to occupation narrative text data. The AI team found
that numerous misspellings of the occupation description terms made the use of automatic
language processing methods impractical (Appendix I). Instead, as described earlier, Wiseyak

74
Inc. used a “list maintenance” method to classify the occupation description terms into the hotel
room cleaning occupation codes. I provided feedback to the AI team, who further refined the
method and re-coded the training data. The AI-coded training data were found to be 98.4%
accurate for coding the Hotel Room Cleaner Occupation variable and 99.4% accurate for coding
the Hotel Room Cleaner Job Title variable. The entire data sample was sent to Wiseyak Inc. to
filter and code the Hotel Room Cleaner Occupation and the Hotel Room Cleaner Job Title
variables using the codebook finalized after coding the training data.
Results of Quality Control Checks on Coded Hotel Room Cleaner Occupation and Job Title Data
A CUNY Graduate School of Public Health and Health Policy (GSPHHP) student researcher
was hired by the CUNY Research Foundation to assist me in performing a 20% quality control
check on the coded responses. In addition, I manually reviewed the AI-coded data for responses
to the Hotel Room Cleaner Occupation and Job Title variables: 33% (7,698) of the entire dataset
for claims with all possible responses for Hotel Room Cleaner Occupation (n=23,070) were
reviewed along with corresponding responses for Hotel Room Cleaner Job Title.
Table 4.1 depicts adjustments made to the codebook as a result of the 20% quality control check
and two manual reviews described above. Occupation terms decreased for response codes
Unknown (n=7) and No (n=4) causing an increase in the Maybe, Question and Misclassified
claims. An improved coding scheme resulted with an increased number of potential hotel room
cleaner occupation terms to research in the future. The data sample was recoded according to the
codebook changes using Excel©2016 software features Filter, Find, Replace and Sort.
Table 4.1 Hotel Room Cleaner Occupation Term Counts:
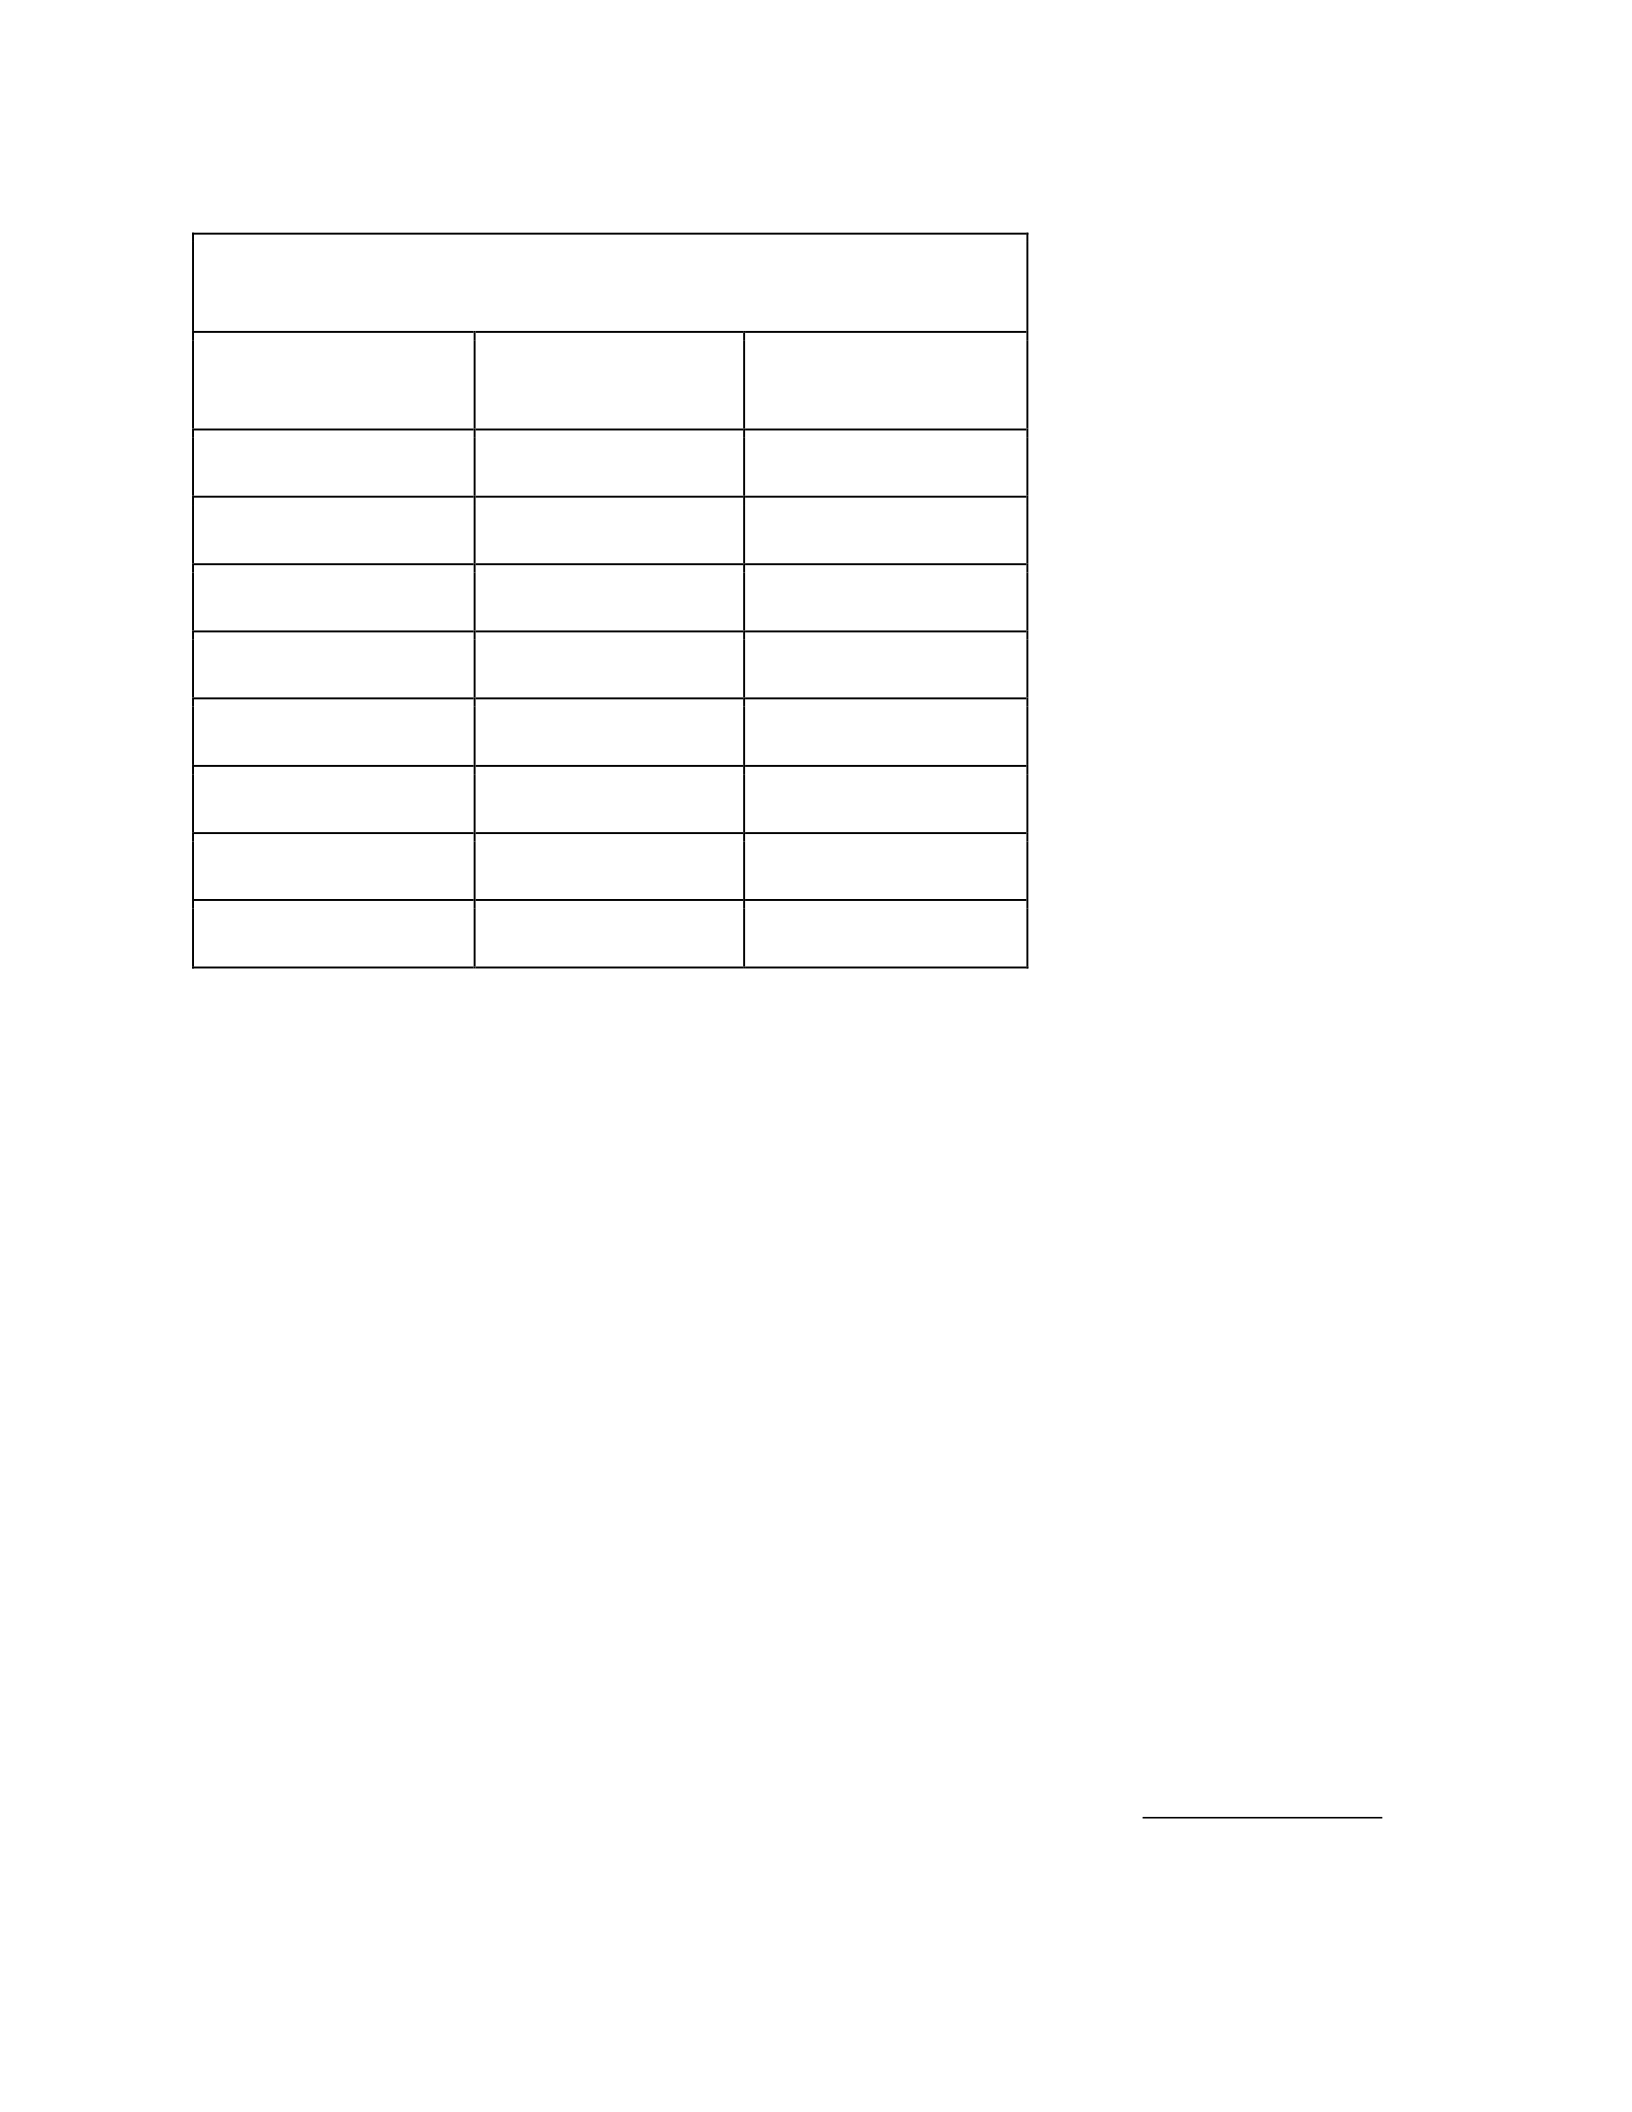
75
Pre and Post Quality Control Checks
Hotel Room Cleaner Occupation Term Counts: Pre
and Post Quality Control Checks
Occupation Term
Original
Coding Decision
Revised Coding
Decision
Yes
184
184
No
1,795
1,791
Maybe
139
141
Question
36
43
Misclassified
6
8
Unknown
55
48
Missing
1
1
Total
2,216
2,216
Creation of the “Female Hotel Room Cleaner Occupation MSD Claims” Analytic Data Sample
All claims not meeting the criteria for a hotel room cleaner were removed from the data sample.
Of the remaining claims, 48% (5,829) of the responses for the Hotel Room Cleaner and Hotel
Room Cleaner Job Title variables were reviewed. The “Female Hotel Room Cleaner Occupation
MSD Claims Study Dataset” contains 12,125 claims for 2007-2016 and is the analytic data
sample for Aim 3A (see Part 2, Descriptive Analyses: Female Hotel Room Cleaner MSD Claims
Data).
Aim 2. Identification of Task at Time of Injury
Creation of the “5-Year Female Hotel Room Cleaner MSD Claims” Data Sample
To achieve Aim 2, the identification of the task at time of injury in female hotel room cleaner

76
MSD workers’ compensation claims data, the “5 Year- Female Hotel Room Cleaner Task at Time
of Injury” data sample was created from the Female Hotel Room Cleaner Occupation MSD
dataset. Study years were reduced to the most recent five years of data, 2012-2016, to reflect
current changes in hotel accommodations and hotel housekeeping work practices.
Creation of the “Task at Time of Injury” Variable and Response Codes
A new variable “Task at Time of Injury” was created and identifies the specific job task the hotel
room cleaner was performing when injured. This new variable is based on narrative text data
from the “Accident Description/Cause” variable. This variable determines whether the claim is
included in this study’s task analysis or for future research. Task codes were created using
seven categories for “Housekeeping tasks” defined in the Cal/OSHA Title 8.3345 Hotel
Housekeeping Musculoskeletal Injury Prevention standard, section (b) Definitions.1 See Study
Variables, Section 3 Methods and additional response codes in the next paragraph for details. All
claims were coded to answer the study research questions, “What is the task at time of injury?”
Two qualified coders with experience in occupational injury research (my dissertation committee
sponsor and myself) coded the same 550 cases drawn from a random sample stratified by year.
This number of cases represents approximately a 15% sample of the estimated final task data
sample. Issues of concern were flagged, disagreements in coding task data that did not meet the
seven task categories were resolved, and new task codes and an initial codebook were created.
A “missing” code (88) was created. “Emergent hazards” were identified such as “making a
rollaway,” resulting in the creation of subclassifications of the relevant seven task categories,

77
e.g., “rollaway (21), “sofa bed” (22), “Murphy Bed” (23) as subclassifications of “making bed”
task (2). The task category “Unknown” (9) was created for data where task was not determined;
multiple subclassifications of “unknown” task codes were created (see details in the “Study
Variables” section). This follows subject matter experts’ recommendations to add “unknown” as
a response category for the task variable since previous researchers coded task as “unknown” for
33% of WCIS cases studied.47
Creation of Artificial Intelligence (AI) Model to Classify and Code Task Data
I provided training subsamples for the AI team to develop a NLP model to filter claims and code
task at time of injury. The training subsample consisted of raw task data from the Accident/
Cause variable (injury description) for 545 hotel room cleaner claims, randomly selected and
stratified by year and broken down by each task category, e.g., 50 claims with task data about
vacuuming (3), 50 claims with task data about moving furniture (7), etc. I used Excel©2016
software features “Filter,” “Find” and “Sort” to select and de-identify the training data before
sending to the AI team.
Based on my feedback and additional training sample data (n=300 claims), the AI team further
refined the model, generating three iterations of the model. The larger the amount of training
data, the greater the accuracy of the NLP application (Appendix I). A “percent confidence level”
column was added by the AI team to indicate the probability that the model predicted the
accurate task code (classification) based on the narrative text in the injury description, e.g., the
model coded a claim for task at time of injury as “bedmaking,” (2) and the narrative text data in
the injury description corresponded to a bedmaking task. The limits of the model to code

78
subclassifications of task categories or to classify the subcategories of unknown responses, e.g., a
narrative text field with only a diagnosis or a part of body injured and no description of the task,
were identified by the AI team and myself. This resulted in the recognition that the “unknown”
(9) code would capture this data broadly, leaving reconciliation of coding the unknown data to
more specific subclasses to be performed possibly in the future. When comparing the coded
responses for Task at Time of Injury variable to the training sample of 200 claims, 90% of the
claims were coded accurately. The codebook was finalized with variables, response labels and
codes, coding rules and justification for codes. The AI model was deemed ready to be run on the
task data sample.
Results of De-identification of Task Data Sample
Before sending the task data sample to the AI team for coding task, the data sample was
deidentified (see Section 3 Methods). Gender terms such as “she” and “her” were extensive in
the narrative text injury descriptions and were the most frequent type of identifiable data. Even
where a worker’s name or the term “she” instead of employee’s name was not used, “her” was
used widespread in the entire task dataset. Paired examples of before and after de-identification
narrative text injury descriptions are included below, the employee’s name removed as needed:
“[employee name] was sweeping balconies when she began to feel pain”
“ee was sweeping balconies when ee began to feel pain”
“while pulling the sofa bed forward with both hands in a guest room, she injured her
right shoulder”
“while pulling the sofa bed forward with both hands in a guest room, ee injured right
shoulder”

79
“[employee name] was cleaning room [number] shower head and felt a sharp pain in her
left calf”
“ee was cleaning room x shower head and felt a sharp pain in left calf”
De-identification for gender terms, in particular, was a lengthy process as the task data sample
sent to the AI team to code included of 8,442 claims, of which 1,490 were “Maybe” and
“Questions” claims.
Results of Quality Control Sampling of Narrative Text Data Classified into Task Categories After
receiving the coded task data from the AI team, I removed 1,490 claims with hotel occupation
coded as Maybe or as Questions as these claims were included so they could be coded for task
for possible future research. Of the 6,952 hotel room cleaner claims remaining (82% of the
original task data sample sent to the AI team), 3,013 (43%) were coded as unknown and were
removed. The remaining 3,939 claims comprise the task data sample that was used to perform
quality control checks on the Task at Time of Injury variable response codes.
Table 4.2 provides the results of the quality control checks on task data for each of the seven task
categories and two subtasks, and by key indicators. Overall, 14.9% of the coded task data was
sampled, with percent quality control checks varying by size of task category as explained in
Section 3 Methods. Over two-thirds (68.3%) of the coded task data sample had claims in the
≥70% confidence level category. The overall estimated accuracy of the coded task data is 84.5%.
Based on these results, I decided to remove all claims that had a task confidence level < 70% to
improve coding accuracy which is supported by the literature (Marucci-Wellman et al., 2017)

80
and was recommended by the AI team. Also, 89% of all claims (using a weighted average) were
deemed as related to hotel room cleaning tasks.
Table 4.2 Results of Quality Control Sampling of Narrative Text Data Classified into Numeric Task Categories, Years 2012-2016
N % %
TASK % QC QC HRC- classified
CATEGORY Code N sample sample related correct
≥70%
conf.
level
%
correct
%
correct
%
correct
≥70%
claims
only
≥70%
claims
correct
clean
1
1,235
20%
247
90%
55%
71.4%
70.7%
19.1%
19.2%
881
622
bedmaking
2
1,424
10%
143
89.5%
80%
69.2%
91.9%
68.8%
46.4%
984
904
vacuum
3
186
15%
29
89.7%
83%
27.6%
100%
85.7%
71.4%
51
51
cart
4
593
10%
61
88.5%
84%
80.3%
89.8%
100%
44.4%
476
427
supplies
5
81
20%
17
70.6%
53%
29.4%
60%
50%
50%
23
13
trash
6
138
15%
21
85.7%
62%
61.9%
100%
n.a.
0%
85
85
move furniture
7
154
15%
23
82.6%
61%
47.8%
73%
n.a.
54.5%
73
53
missing
88
1
n.a.
n.a.
n.a.
n.a.
n.a.
n.a.
n.a.
n.a.
n.a.
n.a.
Subtasks
Rollaway bed
21
24
100%
24
100%
100%
62.5%
100%
100%
100%
15
15
sofa bed
22
103
20%
21
100%
100%
100%
100%
n.a.
n.a.
103
103
%
claims
≥70%
conf.
level
claims
6069%
conf.
level
claims
<60
conf.
level Estimate
claims N*
Estimate
N**

Murphy bed 23 n.a. n.a. n.a. n.a. n.a. n.a. n.a. n.a. n.a. n.a. TOTAL 3,939 586 2,691 2,273
% TOTAL
SAMPLED
OVERALL
14.9%
% ESTIMATED
ACCURACY RATE
OF ESTIMATED
TASK ANALYTIC
DATA SAMPLE
84.5%
*Estimate N >=70% confidence level claims only = result of Column E (n of sample) x Column H (% claims >=70%)
**Estimate N >=70% confidence level claims correct = result of Column I (%correct of >=70% confidence
level claims) x Column L (Estimate N >=70% confidence level claims only)
81
n.a.

83
Creation of the “Female Hotel Room Cleaner Task at Time of Injury” Analytic Data Sample,
Years 2012-2016
Based on the results of the quality control checks on the coded task data, the accuracy and
quality of the coded task data was considered acceptable. The “Female Hotel Room Cleaner
Task at Time of Injury Dataset” consists of 2,629 claims and is the analytic data sample for Aim
3B (see Part 2, Descriptive Analyses: Female Hotel Room Cleaner MSD Claims Data). The steps
to arrive at this dataset from the initial Female Hotel Industry MSD Claims dataset (n=23,070)
and then sequentially from the Female Hotel Room Cleaner Occupation MSD Claims dataset
(n=12,125) was presented in Figure 3.2, page 54, Section 3.
Part 2: Descriptive Analyses of Female Hotel Room Cleaner MSD Injury Claims Data
Aim 3A: Female Hotel Room Cleaner Claimant Demographic, Work and Injury Characteristics
Research Question 1: Can we establish that as an occupation, hotel room cleaners experience
MSD injuries?
Of the 23,070 female hotel industry MSD claims for years 2007-2016, the majority of the
claimants, 52.6%, were hotel room cleaners (n = 12,125).
Research Question 2: Can we characterize hotel room cleaner MSD claims by demographic
factors of the host such as gender and age?
Gender
All claimants were female. The decision to include only female claimants was made when setting
parameters for the hotel industry study dataset. The decision was based on the high percentage of
84
females in the job titles referred to above and the proportion these two job titles accounted for in
claims with hotel room cleaner job titles (Study Dataset, Section 3 Methods).
Age
The mean age of the study population was 43.6 years (SD 10.9) with ages ranging from 18 to 90
years (Table 4.3, page 89). By age group (Table 4.4, page 89), the highest proportion of hotel room
cleaner MSD claims were for claimants aged 45-54 years (33.1%), followed by claimants aged 35-
44 years (28.9%) and 25-34 years (16.8%). The number of claims increased with age group,
peaking in the 45-54 years age group, then decreasing by more than half for those 55-64 years.
The lower numbers observed in the latter age group may reflect the age distribution in the hotel
room cleaner population overall. Unfortunately, I do not have access to such populationlevel data.
Research Question 3: Can we characterize hotel room cleaner MSD claims by work-related
factors of the host such as job title category, e.g., housekeeper, maid, and job tenure?
Job Title Category
The job title of Housekeeper accounts for 58.2% of all claims, followed by Room Attendants with
39.5% (Table 4.5).
Table 4.5 Breakdown of Female Hotel Room Cleaner Occupation by Job Title, 2007-2016
(n=12,125)
Hotel Room Cleaner Job Title
Housekeeper
7,055 58.2
Room Attendant
4,785 39.5
Room Cleaner
84 0.7
Maid
85 0.7
Houseperson
116 0.9
Total
12,125 100
N
%
85
Job Tenure
Findings for mean job tenure are in Table 4.3, page 89 and are expressed using two metrics:
“years” (the time difference in years between Date of Hire and Date of Injury) and “months”
(the time difference in years between Date of Hire and Date of Injury) computed using SAS
INTCK procedure (see Section 3, Study Variables, page 60). The mean job tenure at time of injury
using a “years” metric was 5.2 years (SD 6.6), ranging from 0-62 years. Using a
“months” metric, the mean job tenure at time of injury was 67.9 months (SD 79.9), ranging from
0-746 months. The mean job tenure amount in months is the equivalent of 5.7 years, capturing
five more months of job tenure than the years metric. By job tenure group (Table 4.6), hotel
room cleaners with 2-5 years job tenure accounted for the highest proportion of claims (21.3%).
The 5-10 years and the ≤6 months job tenure groups each accounted for approximately 18% of
all claims. Further research is needed to understand the significance of the tenure group findings
due to the low to mid-tenure groups’ representation in the distribution of hotel room cleaner
claims. These findings may reflect the overall distribution of tenure among the hotel room
cleaner population or could indicate an area of further research.
Table 4.6 Distribution of Female Hotel Room Cleaner MSD Claims by Job Tenure, Californi
Workers’ Compensation Claims, 2007-2016 (n=11,559)
Job Tenure N %**
7 months-1 year 1,170
10.1
1-2 years
1,491
12.9
2-5 years
2,464
21.3
5-10 years
2,116
18.3
10-20 years
1,672
14.5

86
20+ years
564
4.9
*
Missing = 566.
** Percentages may not add up to 100% due to rounding.
Age Group by Tenure Group
The correlation between age and tenure (Table 4.3, page 89) was 0.44 (P < 0.0001) for both
tenure variables (month and year), indicating a medium correlation. Figure 4.1 presents a
grouped bar plot of the seven tenure groups by the eight age groups to better understand age and
tenure in the study sample. The ≤6 months tenure group accounted for the majority of claims for
age groups 18-24 and 25-34 years and ranked second for the 35-44 years age group. The 2-5
years tenure group ranked first for the 35-44 years age group and second for the 45-54 age group.
The 5-10 years tenure group ranked first for the 45-54 age group. The 10-20 years tenure group
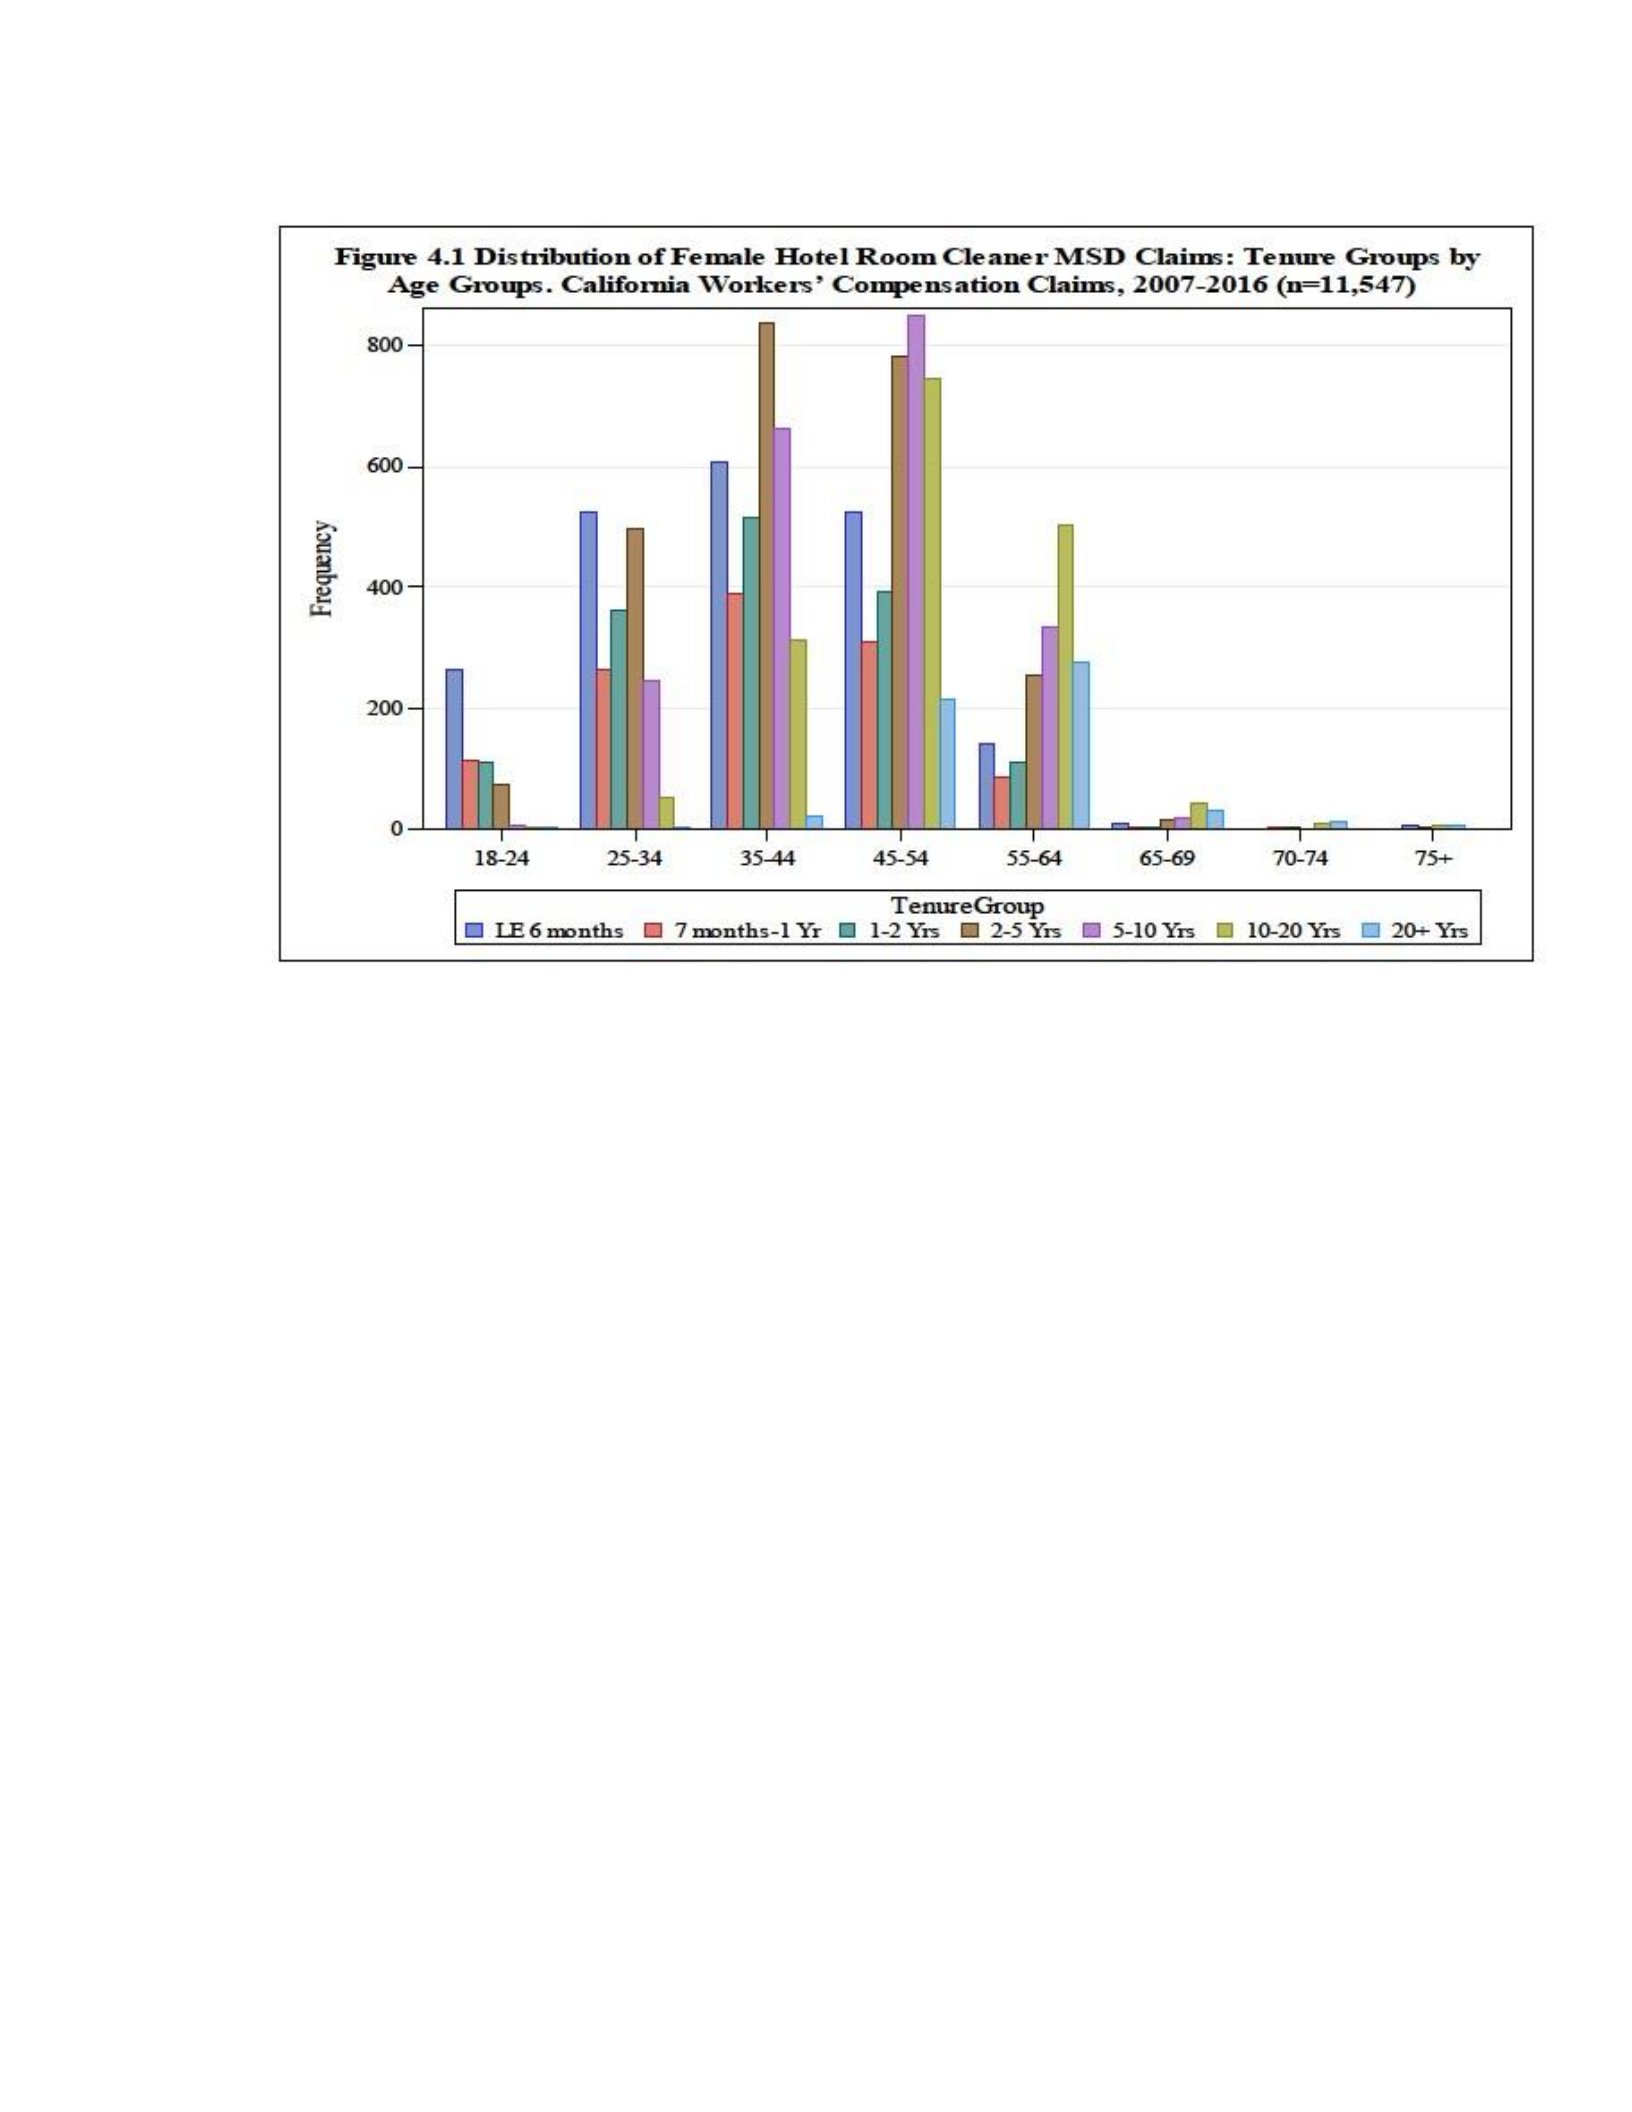
87
ranked third for the 45-54 years age group and accounted for the majority of claims for the 55-64
years age group. The findings by age and tenure groups indicate that lower tenure groups account
for substantial proportions of mid-range age groups. Further analysis is needed to understand age
and tenure group patterns in the data. There is a need to determine whether the prevalence of
injuries for the ≤6 months tenure group across various age groups reflects the actual distribution
of tenure by age group or instead reflects a trend of higher injury prevalence for hotel room
cleaners with less job experience.

88
Research Question 4: What are the leading nature of injury categories found in the claims
data?
Nature of Injury
By Nature of Injury (Table 4.7, page 90), “Strain or Tear” injuries accounted for close to twothirds
of all injuries (64.9%), followed by “Sprain or Tear” injuries with 11.9%
Research Question 5: What are the leading cause of injury categories found in the claims data?
Cause of Injury Category
By Cause of Injury Category (Table 4.8, page 91), “Strain or Injury By” accounted for the overwhelming
majority of injuries (92%). By individual Cause of Injury (Table 4.9), “Strain or
Injury By, NOC” accounted for 27.7% of claims, followed by “Pushing or Pulling” (18.4%), “Repetitive
Motion” (16.6%) and “Lifting” (14.5%).
Table 4.9 Distribution of Hotel Room Cleaner Claimants’ MSD Injuries by Cause of Injury,
California Workers’ Compensation Claims, 2007-2016 (n=12,125) Cause of Injury
N %*
Strain or Injury By, NOC
3,352
27.7
Pushing or Pulling
2,231
18.4
Repetitive Motion
2,017
16.6
Lifting
1,761
14.5
Cumulative, NOC
885
7.3
Twisting
767
6.3
Reaching
635
5.2
Other**
477
3.9
*Percentages may not add up to 100% due to rounding.
**All remaining categories, each of which account for <3% of injuries.
89
Research Question 6: What are the leading part of body injured categories found in the claims
data?
By Part of Body Category (Table 4.10), “Upper Extremities” was the most frequent category, with
40.5% of all claims, followed by “Trunk” (33.2%) and “Lower Extremities” (13.4%).
Table 4.10 Distribution of Hotel Room Cleaner Claimants’ MSD Injuries by Part of Body Category,
California Workers’ Compensation Claims, 2007-2016 (n=12,125) Part of Body Category
N %
Upper Extremities
4,909
40.5
Trunk
4,030
33.2
Lower Extremities
1,626
13.4
Multiple Body Parts
1,201
9.9
Neck
168
1.4
Other*
191
1.6
*All remaining categories, each of which account for <1% of injuries.
By individual Part of Body (Table 4.11), Low Back Area’ accounts for the highest proportion of claims
(27.2%), followed by “Shoulders” (14.3%). Taken together, “Multiple Body Parts,”
“Wrist” and “Knee” account for about one-quarter of remaining hotel room cleaner MSD claims.
Table 4.11 Distribution of Hotel Room Cleaner Claimants’ MSD Injuries by Part of Body, California
Workers’ Compensation Claims, 2007-2016 (n=12,125) Part of Body
N %*
Low Back Area (Lumbar and Lumbo-Sacral)
3,292
27.1
Shoulder(s)
1,732
14.3
Multiple Body Parts (incl. Body Systems and Body Parts)
1,201
9.9
Wrist
877
7.2
Knee
762
6.3

90
Hand (excl. Wrist and Fingers)
459
3.8
Multiple Upper Extremities
445
3.7
Lower Arm
360
3.0
Ankle
346
2.8
Upper Arm (excl. Clavicle and Scapula) 296
2.4
Upper Back Area (Thoracic Area) 248
2.0
*
**All remaining categories, each of which account for <2% of injuries.
Additional Tables: Aim 3A Demographic and Injury Characteristics
Table 4.3 Mean Age and Job Tenure Characteristics of Hotel Room Cleaner Claimants with MSD
Injuries, California Workers’ Compensation Claims, 2007-2016 (n=12,125)
Age at time of injury
N
Mean
(SD)*
Minimum
Maximum
12,109**
43.6
10.9
18
90
Job tenure at time of injury (months)
11,558***
67.9
79.9
0
746
Job tenure at time of injury (years)
11,588***
5.2
6.6
0
62
*SD, standard deviation.
**Missing = 16 (0.13%)
***Missing = 567 (4.68%)
Other**
2,107 17.4
Percentages may not add up to 100% due to rounding.
91
Table 4.4 Distribution of Hotel Room Cleaner MSD Claims by Age Group, California Workers’
Compensation Claims, 2007-2016 (n=12,109)* Age Group
N %*
18-24
597
4.9
25-34
2,039
16.8
35-44
3,496
28.9
45-54
4,009
33.1
55-64
1,782
14.7
65-69
129
1.1
70-74
31
0.3
75+
26
0.2
*Missing = 16 (0.13%)
Table 4.5 Breakdown of Hotel Room Cleaner Occupation by Job Title, 2007-2016 (n=12,125)
Hotel Room Cleaner Job Title N %
Housekeeper 7,055 58.2
Room Attendant 4,785 39.5
Room Cleaner 84 0.7
Maid 85 0.7
Houseperson 116 0.9
Total 12,125 100
Table 4.6 Distribution of Hotel Room Cleaner MSD Injuries by Job Tenure, California Workers’
Compensation Claims, 2007-2016 (n=11,559)
Job Tenure
N
%**
7 months-1 year
1,170
10.1
1-2 years
1,491
12.9
92
2-5 years
2,464
21.
3
5-10 years
2,116
18.3
10-20 years
1,672
14.5
20+ years
564
4.9
*
Missing = 566 (4.7%)
** Percentages may not add up to 100% due to rounding.
Table 4.7 Distribution of Hotel Room Cleaner MSD Injuries by Nature of Injury, California Workers’
Compensation Claims, 2007-2016 (n=12,125)
%*
Strain or Tear
7,864 64.9
Sprain or Tear
1,444 11.9
All Other Specific Injuries, NOC
994 8.2
All Other Cumulative Injuries
933 7.7
Inflammation
340 2.8
Multiple Physical Injuries Only
250 2.1
Other **
300 2.5
*Percentages may not add up to 100% due to rounding.
**All remaining categories, each of which account for <1% of injuries.
N
93
Table 4.8 Distribution of Hotel Room Cleaner MSD Injuries by Cause of
Injury Category, California Workers’ Compensation Claims, 2007-2016
(n=12,125) Cause of Injury Category
N %
Strain or Injury By
11,156
92.0
Miscellaneous Causes
885
7.3
Rubbed or Abraded
71
0.6
Striking Against or Stepping Down 13 0.1
Table 4.9 Distribution of Hotel Room Cleaner Claimants’ MSD Injuries by Cause of Injury,
California Workers’ Compensation Claims, 2007-2016 (n=12,125) Cause of Injury
N %*
Strain or Injury By, NOC
3,352
27.7
Pushing or Pulling
2,231
18.4
Repetitive Motion
2,017
16.6
Lifting
1,761
14.5
Cumulative, NOC
885
7.3
Twisting
767
6.3
Reaching
635
5.2
Other**
477
3.9
*Percentages may not add up to 100% due to rounding.
**All remaining categories, each of which account for <3% of injuries.
Table 4.10 Distribution of Hotel Room Cleaner Claimants’ MSD Injuries by Part of Body Category,
California Workers’ Compensation Claims, 2007-2016 (n=12,125) Part of Body Category
N %
Upper Extremities
4,909
40.5
94
Trunk
4,030
33.2
Lower Extremities
1,626
13.4
Multiple Body Parts
1,201
9.9
Other*
359
3.0
*All remaining categories, each of which account for <2% of injuries.
Table 4.11 Distribution of Hotel Room Cleaner Claimants’ MSD Injuries by Part of Body, California
Workers’ Compensation Claims, 2007-2016 (n=12,125) Part of Body
N %*
Low Back Area (Lumbar and Lumbo-Sacral)
3,292
27.1
Shoulder(s)
1,732
14.3
Multiple Body Parts (incl. Body Systems and Body Parts)
1,201
9.9
Wrist
877
7.2
Knee
762
6.3
Hand (excl. Wrist and Fingers)
459
3.8
Multiple Upper Extremities
445
3.7
Lower Arm
360
3.0
Ankle
346
2.8
Upper Arm (excl. Clavicle and Scapula) 296
2.4
Upper Back Area (Thoracic Area) 248
2.0
Other** 2,107
17.4
*Percentages may not add up to 100% due to rounding.
**All remaining categories, each of which account for <2% of injuries.
Aim 3B: Female Hotel Room Cleaner Claimant Injury Characteristics by Task at Time of Injury

95
Female Hotel Room Cleaner Claimant Task at Time of Injury Dataset, 2012-2016
The Female Hotel Room Cleaner Task at Time of Injury dataset includes 2,628 claims with task at
time of injury identified for the study years 2012-2016; one claim was removed due to injury
missing incident data. All claims in this dataset meet the threshold of belonging to the ≥70%
confidence level category, signifying that the narrative text data describing the injury incident
was correctly classified by task category. This dataset is also referred to as the Aim 3B analytic
data set and answers the research question, “What was the task at time of injury?” Results from
descriptive statistical analyses to characterize MSD injuries in hotel room cleaners stratified by
seven task categories are presented in Tables 4.12-4.15 on the following pages.
Research Question 7: Can we characterize hotel room cleaner MSD injuries by task at time of
injury?
For the Task at Time of Injury dataset overall, bedmaking claims accounted for the highest
percentage of all claims (43.5%), followed by cleaning surfaces (29.9%) and handling linen carts
(17.2%). The remaining 9.4% of claims were distributed among the four remaining tasks in the
following order: collecting and disposing trash (3.3%), vacuuming (2.7%), moving furniture
(2.3%) and moving linen and supplies (1.1%) in and out of guest rooms.
Table 4.12 Breakdown of Task at Time of Injury, Hotel Room Cleaner MSD Claims (n = 2,628)*
Task Category
N**
%
Cleaning Surfaces
785
29.9

96
Making Beds
1143
43.5
Vacuuming
72
2.7
Handling Linen Carts
453
17.2
Moving Linen/Supplies
28
1.1
Collecting/Disposing Trash
86
3.3
Moving Furniture
61
2.3
Aim 3B: Injury Variables Stratified by Seven Task Categories
Nature of Injury Variable
For the Task at Time of Injury dataset overall, by Nature of Injury category, “Strain or Tear” was
the most frequent type of injury accounting for 75.3% of all claims. By task at time of injury, the
Nature of Injury frequencies varied (Table 4.13). “Strain or Tear” injuries were the leading nature
of injury for all tasks ranging from 65.3% while vacuuming to 82.1% for moving linen/supplies.
“Sprain or Tear” injuries ranked second for all tasks except for vacuuming where it ranked third
after “All Other Specific Injuries, NOC” (12.5%). “Sprain or Tear” injuries were most frequent
when handling linen carts (14.6%). “All Other Cumulative Injuries” occurred most often when
vacuuming (5.6%), followed by cleaning surfaces (2.4%). “Inflammation” injuries were the
highest for collecting/disposing trash (3.5%). Hotel room cleaners moving linen/supplies in and
out of guest rooms had the highest frequency of dislocation injuries (3.6%). Both “Inflammation”
and “Dislocation” occurred across cleaning surfaces, bedmaking, handling linen carts and
vacuuming tasks. Moving furniture was the only task associated with “Carpal Tunnel
Syndrome.” Hernia injuries occurred at low percentages yet were associated with three tasks:
vacuuming (1.4%), collecting/disposing trash (1.2%) and handling linen carts (0.9%).

97
Table 4.13 Nature of Injury by Hotel Room Cleaner Tasks, California Workers’ Compensation MSD Claims, 2012-2016 (n=2,628)
Cleaning Surfaces (n = 784)
%*
Making Beds (n = 1,140)
%
Vacuuming (n = 72)
%*
Strain or Tear
74.2
Strain or Tear
76.7
Strain or Tear
65.3
Sprain or Tear
13.0
Sprain or Tear
12.3
All Other Specific Injuries, NOC
12.5
All Other Specific Injuries, NOC
5.9
All Other Specific Injuries, NOC
5.7
Sprain or Tear
8.3
All Other Cumulative Injuries
2.4
Inflammation
1.7
All Other Cumulative Injuries
5.6
Inflammation
2.0
Dislocation
1.4
Inflammation
2.8
Dislocation
1.5
Other**
2.2
Multiple Physical Injuries Only
2.8
Other**
0.9
Missing = 3
Dislocation
1.4
Missing = 1
Hernia
1.4
Handling Linen Cart (n = 452)
%
Moving Linen/Supplies (n = 28)
%*
Collecting/Disposing Trash (n = 86)
%
Strain or Tear
73.2
Strain or Tear
82.1
Strain or Tear
80.2
Sprain or Tear
14.6
Sprain or Tear
10.7
Sprain or Tear
9.3
All Other Specific Injuries, NOC
7.5
All Other Specific Injuries, NOC
3.6
All Other Specific Injuries, NOC
3.5
Inflammation
2.2
Dislocation
3.6
Inflammation
3.5
Dislocation
0.7
All Other Cumulative Injuries
2.3
Hernia
0.7
Hernia
1.2
Other***
1.1
Missing = 1
Moving Furniture (n = 61)
%*
Strain or Tear
78.7
Sprain or Tear
9.8
All Other Specific Injuries, NOC
6.6
Carpal Tunnel Syndrome
1.6
Dislocation
1.6
Multiple Physical Injuries Only
1.6
*Percentages may not add up to 100% due to rounding.
**All remaining categories, each of which account for <1% of injuries.
***All remaining categories, each of which account for <0.5% of injuries.

98
Cause of Injury Variable
For the Task at Time of Injury dataset overall, by Cause of Injury, six subcategories account for
95.7% of all MSD claims: “Strain or Injury By, NOC” (28.1%); “Pushing or Pulling” (24.8%);
“Lifting” (17.8%); “Twisting” (8.7%); “Reaching” (8.3%) and “Repetitive Motion” (8%). The
remaining claims are represented by six other cause of injury categories with small percentages
(<1%), with the exception of “Holding or Carrying” that accounts for 2.3% of all MSD claims.
As with the other injury variables, the distribution of hotel room cleaner MSD claims for Cause
of Injury varies by the Task at Time of Injury category. The tasks with “Pushing or Pulling”
ranking first for cause of injury were handling linen cart (61.5%), moving furniture (45.9%) and
vacuuming (34.7%), followed by making beds (23.3%), moving linen/supplies (14.3%) and
collecting/disposing trash (10.5%) where it ranked third as cause of injury. Lifting was the most
frequent cause of injury for collecting/disposing trash (48.8%), moving linen/supplies (32.1%)
and making beds (26.5%), followed by moving furniture (19.7%) and handling linen carts
(12.8%). Cleaning surfaces was the task with the highest proportion of “Strain or Injury By,
NOC” (45.3%), followed by making beds (26.2%), moving linen/supplies (21.4%) and moving
furniture (18%) where it ranked second. Cleaning surfaces and vacuuming were the tasks at time
of injury with repetitive motion ranked second, 15.7% and 12.5%, respectively. Twisting ranked
fourth for the following tasks: moving linen/supplies (14.3%), cleaning surfaces and making
beds (both 9.9%), collecting/disposing trash (7%) and handling linen carts (4.9%). Bedmaking
had the first three causes of injury with equal prevalence: “Lifting” (26.5%), “Strain or Injury,
By NOC” (26.2%) and “Pushing or Pulling” (23.3%).

99
Table 4.14 Cause of Injury by Hotel Room Cleaner Tasks, California Workers’ Compensation MSD Claims, 2012-2016 (n=2,628)
Cleaning Surfaces (n = 784)
%
Making Beds (n = 1,140)
%
Vacuuming (n = 72)
%
Strain or Injury by, NOC
45.3
Lifting
26.5
Pushing or Pulling
34.7
Repetitive Motion
15.7
Strain or Injury By, NOC
26.2
Repetitive Motion
12.5
Reaching
14.7
Pushing or Pulling
23.3
Strain or Injury by, NOC
12.5
Twisting
9.9
Twisting
9.9
Holding or Carrying
11.1
Pushing or Pulling
5.2
Reaching
6.0
Using Tool or Machinery
11.1
Lifting
5.0
Repetitive Motion
5.3
Lifting
6.9
Other**
4.2
Other**
2.8
Twisting
5.6
Missing = 1
Missing = 3
Reaching
4.2
Other**
1.4
Handling Linen Cart (n = 452)
%
Moving Linen/Supplies (n = 28)
%*
Collecting/Disposing Trash (n = 86)
%
Pushing or Pulling
61.5
Lifting
32.1
Lifting
48.8
Lifting
12.8
Strain or Injury by, NOC
21.4
Strain or Injury by, NOC
11.6
Strain or Injury by, NOC
10.6
Pushing or Pulling
14.3
Pushing or Pulling
10.5
Twisting
4.9
Twisting
14.3
Twisting
7.0
Reaching
4.4
Holding or Carrying
7.1
Holding or Carrying
5.8
Holding or Carrying
3.1
Reaching
7.1
Reaching
5.8
Other**
2.7
Repetitive Motion
3.6
Wielding or Throwing
5.8
Missing = 1
Repetitive Motion
3.5
Moving Furniture (n = 61)
%*
Pushing or Pulling
45.9
Lifting
19.7
Strain or Injury by, NOC
18.0
Repetitive Motion
8.2
Reaching
4.9
Other**
3.3

100
*Percentages may not add up to 100% due to rounding. **All
remaining categories, each of which account for <2% of injuries.

101
Part of Body Variable
Upper Extremities is the most frequently reported Part of Body Category for task dataset claims
(42.2%), followed by Trunk (37.55%) and Lower Extremities (14.33%). Together, these three
Part of Body Categories account for 94.1% of task dataset claims, yet the distribution of claims
by individual part of body varies with each task category (Table 4.15). Lower back injuries were
the leading cause of injury for all tasks with moving furniture having the highest proportion
(47.5%), followed by moving linen/supplies (42.9%), making beds (35.7%) and handling linen
carts (32.5%) among the tasks with higher proportions. Shoulder injuries ranked second for
hotel room cleaners across all tasks with collecting/disposing trash (19.8%), moving linen/
supplies (17.9%), cleaning surfaces (17.15), making beds (16.8%) and vacuuming (16.7%) the
leading tasks at time of injury. Moving furniture, cleaning surfaces and making beds were tasks
where knee and wrist injuries ranked third and/or fourth for hotel room cleaners. Vacuuming
had the highest proportion of hand injuries (9.7%) where it ranked fourth as cause of injury,
followed by cleaning surfaces (5.6%) and making beds (3.6%), ranking fifth for both tasks.
Ankle injuries occurred at low frequency levels yet were common to handling linen carts (6%)
and vacuuming (4.2%). The remaining cause of injuries were distributed among “other”
categories, with “Other – Upper Extremities” the leading “other” cause of injury across all tasks.
Cleaning surfaces (18.9%) was the leading task at time of injury for “Other – Upper Extremities”
as cause of injury, followed by handling linen/carts (14.8%) and making beds (14.2%). Moving
linen/supplies and collecting/disposing trash were the tasks with the highest proportion of “Other
– Lower Extremities” injuries, with 10.7% and 10.5%, respectively. Handling linen carts (7.7%),
moving linen/supplies (7.1%), moving furniture (6.6%), making beds (6.3%) and collecting/
disposing trash accounted for the task at time of injury for “Other – Trunk.”
102
Table 4.15 Part of Body Injured by Hotel Room Cleaner Tasks, California Workers’ Compensation MSD Claims, 2012-2016 (n=2,628)
Cleaning Surfaces (n = 784)
%*
Making Beds (n = 1,140)
%
Vacuuming (n = 72)
%*
Lower Back Area
22.4
Lower Back Area
35.7
Lower Back Area
26.4
Shoulder(s)
17.1
Shoulder(s)
16.8
Shoulder(s)
16.7
Knee
13.0
Wrist
8.9
Multiple Body Parts**
12.5
Wrist
7.0
Knee
5.5
Hand (excl. Wrist and Fingers)
9.7
Hand (excl. Wrist and Fingers)
5.6
Hand (excl. Wrist and Fingers)
3.6
Wrist
5.6
Other - Upper Extremities
18.9
Other - Upper Extremities
14.2
Ankle
4.2
Other - Lower Extremities
6.8
Other - Trunk
6.3
Other - Upper Extremities
13.9
Other
9.0
Other - Lower Extremities
3.9
Other - Lower Extremities
7.0
Missing = 1
Other
Missing = 3
5.1
Other
4.2
Handling Linen Cart (n = 452)
%*
Moving Linen/Supplies (n = 28)
%
Collecting/Disposing Trash (n = 86)
%
Lower Back Area
32.5
Lower Back Area
42.9
Lower Back Area
31.4
Shoulder(s)
12.8
Shoulder(s)
17.9
Shoulder(s)
19.8
Wrist
7.5
Other - Upper Extremities
7.1
Wrist
9.3
Knee
6.4
Other - Trunk
7.1
Lower Arm
7.0
Ankle
6.0
Other - Lower Extremities
10.7
Upper Back Area
4.6
Other - Upper Extremities
14.8
Other - Multiple Body Parts
14.3
Multiple Body Parts**
3.5
Other - Trunk
7.7
Other - Upper Extremities
8.1
Other - Lower Extremities
6.4
Other - Trunk
5.8
Other
5.7
Other - Lower Extremities
10.5
Missing = 1
Moving Furniture (n = 61)
%
Lower Back Area
47.5
Shoulder(s)
14.8
Knee
9.8
Wrist
6.6
Other - Upper Extremities
9.8
Other - Trunk
6.6
Other
4.9

103
*Percentages may not add up to 100% due to rounding. **Includes Body Systems and Multiple Body Systems.

104
Section 5: Discussion and Conclusions
Study Summary
The goal of this dissertation was to establish the occurrence of hotel room cleaner MSDs using
administrative data and in doing so, develop research methods that will aid researchers to
produce science-based evidence necessary for effective intervention development and program
implementation for hotel room cleaner MSD injury control. This goal was achieved through the
study aims by first identifying the hotel room cleaner occupation (Aim 1) at the hotel industry
study population level (n = 23,070) and documenting the occurrence of hotel room cleaner
MSDs using 12,125 California WC claims. Data analysis produced descriptive findings by cause
and nature of injury and part of body injured for this study sample (Aim 3A). Second, by
identifying the task at time of injury by coding tasks from text data using artificial intelligence
methods (Aim 2), leading causes, nature of injuries and part of body were analyzed by each task
(Aim 3B) for the 2,668 claims where task could be coded, providing insights into MSD claim
injuries by task. Though resource intensive, this study demonstrates the potential for this type of
analysis to examine WC data at the occupation and task level for future research.
Summary of Findings
Aim 1: Identification of Hotel Room Cleaner Occupation
It was possible to identify the occupation of hotel room cleaner using narrative text data from the
Occupation Description field. The occupation of hotel room cleaner is comprised of five job

105
titles that originate from the definition of a “Housekeeper” using Cal/OSHA 3345. Using these
job titles, a list of 2,216 occupation terms was reduced to almost 184 terms that were considered
equivalent to a hotel room cleaner occupation. An algorithm was created to triage those claims
that were considered to be “Maybe” (n = 141 terms) or “Questions” (n = 43 terms) when
answering the question, “Is this a hotel room cleaner?” By coding them separately, these claims
are accessible for future research as potential hotel room cleaner claims. A list maintenance
method was applied to code occupation for 23,070 hotel industry MSD claims for years
20072016. These methods are replicable and make it possible for researchers to access the
narrative text data in the Occupation Description field and identify the occupation of hotel room
cleaner in WCIS data. Of the 23,070 hotel industry claims, 52.6% (12,125) are hotel room
cleaners and an additional 12% (2,765) are “Maybe” and “Questions.” Of hotel room cleaners,
the two most frequent job titles were housekeeper (58.2%) and room attendant (39.5%), together
accounting for 98% of the hotel room cleaner claims. The study dataset was limited to females
only. This decision was based on averaging together these two highly frequent job titles which
resulted in 96% of claimants being female.
Aim 2: Identification of Task at Time of Injury
It was possible to identify the task at time of injury by applying machine learning processing
methods to the narrative text data from the Injury Incident Description field. Training data
(sample narrative task data for each task) was provided to the AI team who refined their model in
a series of steps. The Task at Time of Injury variable is comprised of seven task categories that
originate from the definition of “Housekeeping tasks” using Cal/OSHA 3345 and answer the
question “What is the task at time of injury?” Responses classified as “unknown” account for a

106
high proportion (43.6%) of the claims for years 2012-2016. Additional codes were created to
identify subcategories of “unknown” responses for future research purposes, given the high
prevalence of such claims. Quality control checks of the task data used these “unknown” codes
and found “98,” pain/injury/worker motion/diagnosis to be the most frequent. The overall
estimated accuracy of the coded task data is 84%; 89% of claims sampled were deemed to be
related to hotel room cleaning tasks. Based on guidance from the AI team, claims categorized as
having a <70% confidence level (of being classified in the correct task category) were excluded
from the task analytic data sample. Of the coded task data sample, 18.6% fell into this category,
reducing the task data sample size further. The Aim 3B task analytic data sample includes 2,628
claims (one claim removed due to a missing injury incident description) which represents 37.8%
of hotel room cleaner MSD claims for years 2012-2016 (n = 6,952).
Aim 3A: Female Hotel Room Cleaner Claimant Demographic and Injury Characteristics
For the Aim 3A analytic data sample, years 2007-2016, there were 12,125 claims. By Nature of
Injury, “Strain or Tear” injuries accounted for close to two-thirds of the sample, followed by
“Sprain or Tear” injuries (11.9%). By Cause of Injury, “Strain or Injury By, NOC” (27.7%),
“Pushing or Pulling” (18.4%), “Repetitive Motion” (16.6%) and “Lifting” (14.5%) were the
leading causes. By Part of Body Category, “Upper Extremities” was the most frequent category
(40.5%), followed by “Trunk” (33.2%) and “Lower Extremities” (13.4%). By individual Part of
Body, Low Back Area accounts for the highest proportion of claims (27.2%), followed by
“Shoulders” (14.3%). Taken together, “Multiple Body Parts,” “Wrist” and “Knee” account for
about one-quarter of remaining hotel room cleaner MSD claims.

107
Aim 3B: Injury Variables Stratified by Seven Task at Time of Injury Categories
The Female Hotel Room Cleaner Task at Time of Injury analytic data sample, 2012-2016, has
2,628 claims for years 2012-2016. Bedmaking (43.3%), cleaning surfaces (29.9%) and cart
handling (17.2%) were the leading tasks at time of injury. By Nature of Injury, “Strain or Tear”
injuries accounted for three-quarters of the task dataset overall. By task, the prevalence of “Strain
or Tear” injuries ranged from 65.3% for vacuuming to 82.1% for moving linen/supplies. “Sprain
or Tear” injuries ranked second for all tasks, except vacuuming where it ranked third.
By Cause of Injury in the task dataset overall, the leading three causes are “Strain or Injury By,
NOC” (28.1%); “Pushing or Pulling” (24.8%); and “Lifting” (17.8%). “Twisting,” “Reaching”
and “Repetitive Motion” each account for 8% of claims. For specific tasks at time of injury,
cause of injury varied. “Pushing or Pulling” ranked first as a cause for cart handling, moving
furniture and vacuuming and ranked third for bedmaking (23.3%), moving linen/supplies and
collecting/ disposing of trash. Lifting was the most frequent cause of injury for collecting/
disposing trash (48.8%), moving linen/supplies (32%) and making beds (26.5%), followed by
moving furniture (19.7%) and handling linen carts (12.8%). Cleaning surfaces was the task with
the highest proportion of “Strain or Injury By, NOC” (45%), followed by making beds (26%),
moving linen/supplies (21%) and moving furniture (18%) where it ranked second. Cleaning
surfaces (15.7%) and vacuuming (12.5%) were tasks where repetitive motion ranked second.
Although cause of injury varied by task, it is important to recognize that hotel room cleaning
involves all seven tasks and together can have a cumulative effect resulting in injuries.

108
Upper Extremities is the most frequently reported Part of Body Category for task dataset claims
(42%), followed by Trunk (37.5%) and Lower Extremities (14%). Lower back injuries were the
leading cause of injury for all tasks with moving furniture having the highest proportion (47.5%),
followed by moving linen/supplies (42.9%), making beds (35.7%) and handling linen carts
(32.5%). Shoulder injuries ranked second for hotel room cleaners across all tasks with
collecting/disposing trash (19.8%), moving linen/supplies (17.9%), cleaning surfaces (17.15),
making beds (16.8%) and vacuuming (16.7%) the leading tasks at time of injury. Moving
linen/supplies (10.7%) and collecting/ disposing trash (10.5%) were the tasks with the highest
proportion of “Other – Lower Extremities” injuries.
Significance of Findings
This is the first time WCIS data have been sorted using the Cal/OSHA 3345 definitions as a
framework for both occupation and injury incident (task) narrative text descriptions and that list
maintenance and machine learning processing methods have been applied to WCIS data. These
methods allow for a systematic, replicable and valid approach to transforming narrative text data
into quantitative data, useable for data analysis by future researchers.
These findings establish, using state-level administrative data, that hotel room cleaners
experience MSD injuries and furthermore, account for 2.3 times as many claims (52.6%) as
would be expected given the proportion of the hotel workforce represented by this occupation
(23%).13 There are an additional 12% of claims that are potentially hotel room cleaners, the

109
“Maybe” and “Questions” claims which could bring the hotel room cleaner proportion close
to two-thirds (64.6%). This finding is supported by previous researchers identifying higher
MSD injury rates for hotel housekeepers among hotel workers, high prevalence rates for
musculoskeletal pain using survey data, high risk for low back disorders using biomechanical
evaluations and a high incidence rate using the BLS’s Maids and Housekeeping Cleaners
occupation category, among all workers with MSDs.6,7,9,10,16,46 This is a significant finding
indicating a need to track MSD injuries (surveillance) occurring to hotel room cleaners
(occupation) and to implement interventions at the employer-level (hotel industry) and
government-level (enforcement by Cal/OSHA), carried out at the hotel level (worksite and
employee).
When analyzing 2007-2016 claims (n = 12,125) by Part of Body Category (POB CAT), instead
of individual Part of Body (POB), “Upper Extremities” (40.5%) ranked first followed by
“Trunk” (33.2%), highlighting the importance of upper extremity injuries overall. When
analyzed by POB, “Low Back Area” ranked first and “Shoulders” ranked second. Similar results
were reflected in the smaller task at time of injury dataset for years 2012-2016 and are supported
by previous research.10 By analyzing the claims at the POB level, it is possible to identify
individual upper extremity categories such as “Wrist” (7.2%) and four other upper extremity
POB totaling 12.9%., triggering biomechanical studies and interventions specific to work factors
affecting these parts of body. The POB CAT lens versus the POB lens, shifts the focus from part
of body level to risk factor level, pointing to the need for a comprehensive intervention program
to prevent upper extremity MSD injuries. Such a program needs to recognizes the use of
different upper extremity POB by task and the presence of corresponding biomechanical forces

110
and impact on muscle groups. These observations by POB CAT support concerns expressed
earlier in this dissertation for further research on upper extremity injuries in hotel room cleaners.
Across the seven hotel room cleaner task categories for the Female Hotel Room Cleaner Task at
Time of Injury, 2012-2016 study population (n = 2,628), “Pushing or Pulling,” “Lifting” and
“Strains or Injury By” were the leading causes of injury, respectively. This finding is supported
by similar findings from previous research and by studies in a systematic review of pushing and
pulling forces that found an association with musculoskeletal injuries to the upper extremities,
including shoulders which are reflected in the POB finings in the preceding paragraph.11,101
These leading causes of MSD injury support the justification for the promulgation of Cal/OSHA
3345 which recognizes ten risk factors for an MSD injury including “(6) pushing and
pulling”;
“(4) lifting or forceful whole body or hand exertions”; and others that contribute to strains, “(2)
prolonged or awkward static postures; (3) extreme reaches and repetitive reaches above shoulder
height”. These findings are supported by biomechanical studies that identify lifting rate and
forward bending as key risk factors for low back injuries in hotel room cleaners.9 Given that the
leading causes of hotel room cleaner MSD injuries are addressed by Cal/OSHA 3345, these
findings also justify the elements of the standard including performance of a worksite evaluation,
injury investigation, identification of solutions and the active participation of workers and their
union representative.102 The dissertation findings also point to the need to address these causes of
injury by task when developing safe work practices and interventions and when training on them
as “pushing and pulling” occurred at high frequency for cart handling and also occurred for
bedmaking, as one of the three causes that occurred at similar frequencies.

111
Most tasks had one predominantly leading cause of injury and then substantially lower second
and third causes, followed by a sharply diminished prevalence of other causes. Bedmaking was
the only task that the first three causes of injury had equal prevalence: “Lifting” (26.5%), “Strain
or Injury, By NOC” (26.2%) and “Pushing or Pulling” (23.3%). This finding is extremely
significant because it points to three leading causes, each different than the other from a
biomechanical perspective and each raising unique research questions in search of appropriate
solutions. For example, the use of both fitted sheets and bedmaking lift tools reduced mattress
lifting by 48% in a study of hotel room cleaners.45
The use of the Cal/OSHA 3345 standard as a framework for identifying, classifying and coding
narrative text data into occupation and task at time of injury categories, the creation of an
algorithm for filtering questionable hotel room cleaning occupation terms and the application of
list maintenance and machine learning process methods applied were successful. Occupation and
task data about hotel room cleaner MSD injuries are accessible and useable for quantitative data
analysis, a significant finding of this dissertation. Study findings help point to risk factors of and
solutions to hotel room cleaning MSD injury exposures, providing valuable information needed
for injury prevention, including some never having been reported in the literature to date.
Study Strengths
This study builds on the methods of previous researchers using WCIS data and results in more
expansive findings using different methods directly relevant to hotel room cleaner work
organization for occupation and task, and in certain analyses, using larger sample sizes.11,47 The

112
importance of this study is that some of the major methodological obstacles have been identified
and ways to reduce those obstacles have been created, paving the way for further development
and refinement.
The most significant strength of this dissertation is that with support from the AI team, I was
able to develop methods to overcome the obstacles presented by the narrative text data and using
these methods, workers’ compensation claims can be used to create surveillance systems to
monitor the impact of the Cal/OSHA 3345 hotel housekeeping MSD injury prevention standard
over time. In addition, these methods can be used to further the research by injury variables and
task that was begun here. Important information about an occupation with a high prevalence of
MSD claims was accessed and gives insights into causes and parts of body injured which may
trigger intervention studies.
This dissertation is innovative in several ways in how the methods were applied to the
occupation and task narrative task data. First, definitions from Cal/OSHA 3345 Hotel
Housekeeping Musculoskeletal Injury Prevention standard were used as the framework to sort
occupation terms by the hotel room cleaner job titles. Where there were questions about sorting
the occupation terms into hotel room cleaner job titles, an algorithm was created to triage
occupation terms deemed “Maybe” or “Questions” in separate categories and not included as
hotel room cleaners but accessible for future research. Second, to the best of my knowledge, this
is the first study of hotel room cleaner California WCIS claims applying list maintenance
methods to occupation terms and transforming narrative text injury incident description data
using machine learning process methods into structured task data that can be used for

113
quantitative analysis. These methods are systematic, replicable and valid (Appendix I). Another
study strength is that starting the data analysis at the hotel industry level, followed by the hotel
room cleaner level and then by the hotel room cleaner task level allowed for important study
findings from a macro-level to a micro-level:
• the over-representation of hotel room cleaners (52.6%) in the Female Hotel Industry
MSD Claims, 2007-2016 study population (n = 23,070) compared to accounting for
23% of a hotel’s workforce, a 130% higher representation;14
• “Upper Extremities” identified as the leading part of body category for the ten-year
Female Hotel Room Cleaner Occupation MSD Claims, 2007-2016 study population (n =
12,125);
• “Pushing or Pulling,” followed by “Lifting’, and “Strains or Injury By” as the leading
cause of injuries across seven hotel room cleaning tasks for the Female Hotel Room
Cleaner Task at time of Injury, 2012-2016 study population (n = 2,628); and
• Bedmaking as the only task where the first three causes of injury had equal prevalence:
“Lifting” (26.5%), “Strain or Injury, By NOC” (26.2%) and “Pushing or Pulling”
(23.3%).
A strength of this study is that by following SMEs advice on creating an “unknown” response
code, it is possible to address the limitations of excluding this data in the Aim 3A and 3B
analyses. Having already created codes for subcategories of the “unknown” responses and
having coded them by task at time of injury, it will be possible for future research to analyze
these claims using the same variables as in Aims 3A and Aim 3B.
Similarly, having created codes for potential hotel room cleaner claims, using “Maybe” and

114
“Questions” code and having coded them by task at time of injury, it will be possible for future
research to analyze these claims using the same variables as in Aims 3A and Aim 3B to see how
these claims may differ from the rest of the dataset or on the contrary, identify the associated
occupation terms as belong to the hotel room cleaner category and increasing the proportion of
hotel room cleaners with MSD claims to 64% of the hotel industry WC dataset, close to triple the
expected proportion given the previously stated representation of hotel room cleaners in a hotel
workforce of 23%.14
Study researchers have recommended manually coding data with a 30% confidence level as MLP
modes are less successful coding such data.94 Although the dissertation timeline did not allow for
such manual coding, a strength of this study is that the AI team and I addressed this by excluding
the 30% confidence level claims from the dataset for analysis. An easy first step to improve the
quality of data in the task dataset and to increase the sample size of the task dataset, would be to
code these claims.
Study Limitations
Limits on the sample size of the Aim 3B task analytic data sample. The “Task at Time of Injury”
data sample size was limited by: a) the number of years in the study period; b) the proportion of
the claims classified into task categories that were in the <70% confidence level category and
were excluded from the task analytic data sample; and c) the proportion of the claims classified
into task categories that were coded “unknown” and were excluded from the task analytic data
sample. These limitations introduce bias for the latter two limitation. For claims with <70%

115
confidence level cannot be expected to occur equally across all task categories as the quality of
the data determines the likelihood of accurate classification resulting in more easily identifiable
narrative text, e.g., bedmaking will be classified and less easily identifiable narrative text will
have a lower confidence level, e.g., cleaning surfaces. In the task dataset this occurred with a
lower percentage of claims with “Cleaning Surfaces” included after removing the <70%
confidence interval claims. This results in a skewing of the representation of claims with
“Cleaning Surfaces” as a task at time of injury category, resulting in an overrepresentation of
bedmaking claims. For claims with “Unknown” response codes that fell into the category of
medical diagnoses, one could theorize that these are more severe injury cases since a medical
diagnosis has been identified and there is a bias that they are being excluded for task data
analysis. Both of the examples, point to the value of identifying the proportions of the dataset
represented by the different “unknown” categories and the possible recoding of the claims
manually, as suggested in the literature for more challenging narrative data.60,86
Another major limitation was that occupation and task were narrative text data fields requiring
extensive work to transform the data usable for data analysis. Developing methods, creating
training data and applying list maintenance and machine learning processing techniques (Section
3 Methods) was time-consuming, slowing down the research timeline. In addition to data
transformation, performing the corresponding quality control checks of the data classified into
task categories at each step was a lengthy process.
Limitations of extrapolating study findings to the overall hotel room cleaner population in
California. This is a self-selected population – workers who filed a workers’ compensation
claim. Moreover, there is substantial under-reporting of work-related injuries to employers by

116
hotel room cleaners and an even lower rate of filing workers’ compensation claims by this
occupation group, with one-third of claims rejected.5-7 Thus it is not known how generalizable
these findings are to the overall hotel room cleaner population in California.
Time and funding constraints on improvement of the machine learning process model. With more
resources, a more effective model may be developed resulting in more claims with a ≥70%
confidence level. This would increase the task sample size and present findings that reflect better
the actual claims data. Currently, there is an under-representation of the cleaning tasks due to that
task having a high percentage of claims with <70% confidence level. Manually coding claims
with a ≤30% confidence level is a recognized best practice and is an alternative to an improved
model.94 Also, the correct classification for these claims is easy to identify and recode.
Lessons Learned
Using lessons learned from carrying out this study, approaches to address the study limitations
for future analyses are detailed below.
Expand the number of years in the study period to 2007-2016, increase the analytic sample size
The purpose of limiting the task study period to 2012-2016 was so that the injury incident data
would reflect the most recent five years of hotel accommodation trends and work practices that
result in injury, e.g., thick duvets, high thread-count sheets and more pillows. Although the
reasoning for limiting the data to the most recent five years was valid, in practice, the injury
incident descriptions lacked the level of detail needed to detect recent hotel industry luxury

117
accommodations and work practices. Therefore, adding earlier years of data is recommended.
Estimating the sample size for ten years of data involves multiple steps. Before excluding the
claims with <70% confidence level and the claims coded as “unknown,” the 5-Year Female
Hotel Room Cleaner MSD Claims dataset includes 6,952 claims. After removing 3,013 claims
coded as “unknown” (43%), 3,939 claims remained. Of these, 1,310 (33%) claims with a <70%
confidence level of task classification were removed, leaving 2,629 claims. If we apply the same
steps above to the ten-year “Female Hotel Room Cleaner MSD Claims” study population
(n=12,125), we can estimate that 43% of claims would be classified as “unknowns” (n = 5,214)
and removed. Of the remaining 6,911 claims, there are 2,280 (33%) claims estimated to be
removed for having <70% confidence level. This leaves an estimated 4,631 claims for the Aim
3B task analytic data sample years 2007-2016, a 43% increase over the 2012-2016 sample size (n
= 2,629). This provides a substantial increase in sample size for data analysis for future research.
De-identification of the WCIS data by CA-DWC as part of providing data extraction
De-identification of the numeric data could be performed by the CA-DWC with guidance from
the researcher, e.g., request that a tenure variable be created using date of hire and date of injury
variables, and provide a sample to the researcher with the original variables and the new tenure
variable results. Of the two de-identification issues mentioned above, the de-identification of the
narrative text data was the most time consuming and also the most disconcerting because of the
failure to meet HIPPA’s Safe Harbor requirements to protect confidential information about the
employee.97 For the numeric data, multiple steps in SAS (Section 3 Methods) to create new
variables (e.g., tenure) and then remove original variables, e.g., date of injury, date of hire,
birthdate, zipcode. De-identification of the narrative text included removing gendered terms,

118
diagnoses, names, ages, and court case numbers at the most basic level. Additional steps were
taken to maintain the integrity of the data. Claims with “sheets” in the injury incident description
were removed before the rest of the dataset was de-identified for the term “she”. Next, claims
with “sheets” were de-identified separately and when returned to the dataset. This way, the word
“sheet” remained intact and did become “et,” allowing for future research on fitted sheets or
changes in tucking styles.
De-identification of the narrative text data should be performed before providing data extraction
to researchers. None of the data I listed under narrative text data is necessary to be obtained from
the narrative text injury incident description field. Diagnoses is collected in a dedicated question
on the FROI and is obtained through a separate request from the agency. Although de-identifying
the data would add additional costs to the data extraction charge, I believe most researchers
would consider it worth the extra expense and I would expect that the CA-DWC programmers
would be more qualified to perform the de-identification than the average researcher.
Improving the Narrative Text Occupation and Injury Incident Descriptions Data
The “Occupation Description” data can be improved substantially by adding a new variable,
“SOC Code,” as detailed in Table 5 and is supported by the literature.91
The Injury Incident Description data would be improved by the CA-DWC (the “agency”)
implementing a training and monitoring program for employers on how to complete the
questions detailed further under the next heading. The agency would screen industries with
higher rates of employers not filling out the Injury Incident Description field correctly. The
agency would train these employers on proper ways to provide the information and track the

119
employer’s forms for a certain number of years to improve their data. By targeting the hotel
industry and identifying what size employers are most frequently failing to complete the “Injury
Incident Description” field correctly, CA-DWC could have an impact on improving the quality
of the narrative text data at the hotel industry level and not just at the employer level. This is key,
because short of creating a list of tasks for each industry and creating a “Task at Time of Injury”
variable to use along with the narrative text injury incident information, researchers are
dependent on this text field for key information. The task framework from my dissertation is an
example of a systematic, replicable and valid method, limiting bias from subjective judgement.
Conclusions
This study demonstrates that WCIS data can serve as surveillance data, although with serious
challenges due to two key data fields comprised of narrative text: “Occupation Description” and
“Injury Incident Description.” This dissertation proves that California WC data, with the
application of certain research methods and MLP techniques, can be used to identify at risk
occupations and tasks that need to be addressed by workplace and government interventions.
Importantly, this study supports that hotel room cleaners are an occupation with increased
prevalence of MSD injuries, 2.3 times the expected proportion when compared to the percent of
the hotel workforce they represent. Specific tasks are broken down by cause of injury, providing
new insights on risk factors and job hazards in need of solutions and development of
interventions. This dissertation also demonstrates the multiple causes of injury of each of the

120
seven hotel room cleaning tasks, highlighting three key causes: straining, lifting and pushing or
pulling. These findings support the inclusion of these three key causes as risk factors in
Cal/OSHA 3345 and provides further justification overall for the promulgation of this standard.
Cal/OSHA 3345 requires hazard control programs and interventions by the hotel industry and
government agency enforcement by the California Department of Occupational Safety and
Health.1,103 This analysis gives insight to the multiple exposures experienced by hotel room
cleaners as all seven tasks comprise hotel room cleaning work and can have a cumulative impact
on injury causation.
The study findings are supported by peer-reviewed literature published over the past twenty
years, along with biomechanical studies and hotel room cleaner and union organizer testimony
for the past fifteen years about the hazards of hotel room cleaning and recommended solutions.
Fortunately for the California hotel room cleaner workforce, their participation and that of their
union representatives in identifying hotel room cleaning hazards and solutions is codified in
Cal/OSH 3345, the only state with such a regulation. This dissertation contributes: 1) new
methods to access key information for regulators and researchers to protect hotel room cleaners
from MSD injuries and 2) new findings to guide employers to comply with Cal/OSHA 3345 and
to assist Cal/OSHA in enforcing its comprehensive state-wide regulation.
Future Direction
WCIS data provides useful and important information about MSD injuries including injury
characteristics and task at time of injury. Improvements in how the data is collected by the CA-
DWC is needed. Study findings indicate the need for further intervention research

121
Policy Recommendations for Improving CA-WCIS Data for Prevention Research
Four main problematic issues were encountered in the WCIS data that need to be addressed:
The lack of standardized occupation codes for the claimant. The lack of occupation codes limits
the ability of researchers to access the data to for quantitative data analysis and do so in a
uniform and systematic way. Methods used to ameliorate the problem of narrative text data are
time-consuming, costly to the researcher in human and financial resources, can introduce errors,
are dependent on the subjective judgement of the researcher and limit the comparability of
findings by different researchers who apply unique frameworks for sorting and/or coding the
narrative text occupation data. Even though occupation terms from Cal/OSHA 3345’s definitions
provided a practical framework for sorting 2,000 occupation terms into about 200 hotel room
cleaner occupations and five related job titles, this method is an example of a state-by-state
solution. Currently, this type of research is limited to individuals who have the time and the
resources to perform the time-consuming tasks explained in Section 3 Methods.
Lack of information about the activity/task at time of injury. Questions 22 through 26 from Form
5020 (Appendix B) ask about the event/exposure, i.e., location, equipment/materials/chemicals,
activity and sequence of events. Answers to these questions, when taken together, can provide a
robust description of the activity/task at time of injury. Yet despite these questions, 43% of the
6,952 hotel room cleaner claims coded for task were coded as “unknown.” This study finding is
30% higher than findings that reported 33% unknown for hotel room cleaner injury descriptions
using WCIS data.47 Although the employer took the time to fill out the field, the information
122
provided was not pertinent and hence, not usable. Numbers and percentages are available for a
breakdown of “unknowns” by response codes for quality control samples.
The three main categories of injury incident description data coded as “unknown” are: a) use of
generic phrases, e.g., “while cleaning a room, employee hit head …..” or “during regular duties,
employee hurt back…..,”; b) stating “pain” or part of body; and c) stating the diagnosis, all of
which do not without provide any additional information.
Inclusion of identifiable information in the injury incident descriptions field. Despite the
requirements of HIPPA’s Safe Harbor clause (Section 3 Methods) to protect the employee’s
identity, three main categories of sensitive information about the claimant were encountered in
the injury incident description data (in order of frequency): a) gendered terms, e.g., “she,”
“her,”.; b) medical diagnoses; and c) names (worker/supervisor/ hotel/clinic), injury date, court
case numbers and employee age.97 Even the Employer's Report of Occupational Injury or Illness
Form 5020 (Appendix B) uses gendered terms in its own example for question 26.
Below are specific recommendations for each policy issue identified (Table 5).
Table 5. Policy Recommendations for Improving CA-WCIS Data for Prevention Research
Issue Specific Policy Recommendation
1.The lack of standardized occupation a. Utilize the Office of Management and Budget’s
codes for the claimant Standard Occupational Classification (SOC) system
codes to provide uniform, quantitative data. See
SOC code 37-2012, Maids and Housekeeping
Cleaners (Section 1 Introduction).
b. Maintain use of WCIS Data Element No. 60
Occupation Description (Appendix E). SOC-coded
data can provide first-tier information to identify

123
the occupation of Maids and Housekeeping
Cleaners. Narrative text field can provide secondtier
information, e.g., job titles that may represent
differences in work organization factors that impact
the injury experience, e.g., night cleaners (night
shift), housepersons (extra dirty rooms).
2. Lack of information about the a. DWC must educate employers on the
importance activity/task at time of injury of questions 22-26 and provide training
materials on how to complete those data fields, including examples of correct and
incorrect responses.
b. DWC needs to train employers on the correct
field to enter a POB as a response (question 19).
c. DWC needs to train employers on the correct
field to enter a medical diagnosis as a response
(question 19).
3. Inclusion of identifiable information DWC needs to educate employers: in the
injury incident descriptions field: a. on the content of the Safe Harbor clause;
b. on the importance of not including gendered
terms and medical diagnoses information in the
injury incident description field; and
c. by providing employers examples of correct and
incorrect responses.
Intervention Recommendations for Prevention of Hotel Room Cleaning Injuries
Three key intervention recommendation categories were identified:
Full Implementation of Cal/OSHA 3345 by Hotel Employers and Enforcement by Cal/OSHA
Cal/OSHA 3345 (Appendix H) is designed to prevent hotel room cleaning MSD injuries and
does so through key elements, including: an injury and illness prevention plan, a worksite
124
evaluation, identification of risk factors and solutions, injury reporting, communication program,
training of housekeepers and supervisors, posting worksite evaluation results and maintain
records and making them available to workers and their union representatives. Many of the
elements require the active participation of hotel housekeepers and their union representatives.
The first intervention I recommend to focus on is the widespread implementation of this
comprehensive MSD injury prevention standard by hotel employers, along with the active
enforcement of the standard by Cal/OSHA. Although additional interventions are needed specific
to hotel room cleaning tasks, there is sufficient information available for employers to comply
with Cal/OSHA 3345 standard, including resources in the standard’s non-mandatory Appendix A
(Appendix B), an intervention study on bedmaking and a recently published book chapter on
ergonomic hazards in the hospitality industry focusing on key job titles.45,104
Extensive Training at Key Intervals in a Hotel Room Cleaner’s Tenure
This study found a high percent of claims for newly-hired employees with ≤6months (18%)
tenure and for low-range experienced employees in the 2-5 years (21.3%) tenure groups. A
review of existing risk factors, followed-up by an inventory of interventions, and implementation
of trainings programs is needed to target these two employee groups to prevent MSD injuries

