


Evangelical Families’ Experiences of Mental
Health Challenges
Chapter 1: Introduction to the Study
Christians in Evangelical faith communities differ in their responses to a person’s
mental distress experiences. The more conservative the doctrines and the more literal the
interpretations of the biblical texts in a faith community, the more stigmatizing are
congregants’ attitudes toward individuals experiencing mental distress (Adams et al.,
2018; Freeman & Baldwin, 2020). Regardless of their status as clergy members or
congregants, Evangelical Christians’ religious beliefs influence their conceptualization of
mental distress, their attitudes toward those living with mental distress, and the treatment
approaches they prefer (Hodge et al., 2020; Jones et al., 2012; Sullivan et al., 2014).
Many congregants and clergy members hold stigmatizing views about mental
distress, attributing its causes to a person’s moral failures or spiritual deficiency (Avent et
al., 2015; Freeman & Baldwin, 2020; Jones et al., 2012; Santos & Kalibatseva, 2019;
Stanford & Philpott, 2011). Additionally, church leaders in many Christian faith
communities allocate limited financial and human resources to care for those in need of
mental health assistance because of the lack of adequate knowledge about mental distress
(Rogers et al., 2012; Stanford, 2007; Stetz et al., 2011; Wong et al., 2018). As a result,
families living with mental distress may not have the social support and mental health
care they need (Rogers et al., 2012; Stetz et al., 2011; Wesselmann et al., 2015;
Wesselmann & Graziano, 2010). These perceptions and attitudes about mental distress

directly affect the mental health experiences of families and individuals, namely, stigma,
the nature and quality of support they receive, and how they meet their mental health
needs (Baldwin & Poje, 2020; Freeman & Baldwin, 2020; Rogers et al., 2012;
Wesselmann et al., 2015); consequently, many professed Christians living with mental
distress and their family members continue to struggle to feel accepted and included in
the life of the faith communities to which they claim membership (Brinkley & Kaul,
2014; Corrigan, 2020; Stetz et al., 2011). They may also encounter stigma, indifference,
and alienation within their faith communities (Rogers et al., 2012; Stetz et al., 2011;
Wesselmann et al., 2015; Wesselmann & Graziano, 2010).
Support services such as mental health counseling are available for families
experiencing mental distress outside of faith communities. Though Evangelical Christians
are generally open to receiving counseling, they prefer counselors who share their
religious convictions (Crosby & Bossley, 2012; Rogers et al., 2012). Their religious
beliefs determine their use or rejection of professional counseling, and often, the stricter
their understanding of the biblical texts, the less likely Evangelical Christians will seek
treatment from professional counselors (Crosby & Bossley, 2012). Reluctant to seek
professional counseling, Evangelical Christians resort to spiritual or biblical counseling
from their trusted clergy members (Harris et al., 2016; Thurston & Seegobin, 2014).
Despite the awareness of these families’ challenges, there is a gap in the literature
regarding their lived mental distress experiences, daily challenges, mental health needs,
and overall functioning. Learning about family members’ everyday experiences of

another person living with mental distress can increase the understanding of how they
adapt, cope, or address their challenges. Borg et al. (2009) suggested that such
individuals’ perspectives contain rich details about mental distress. Although discovering
those perspectives requires laborious work since they are buried under mundane everyday
activities, they provide accurate knowledge about mental distress stemming from a
person’s concrete life circumstances (Borg et al., 2009).
For mental health counselors, increased awareness and knowledge of Evangelical
families’ mental distress experiences can expand their understanding of this diverse client
population’s mental health needs. Although counselors are steadily showing appreciation
for the value of clients’ religiosity and its impact on the counseling process, many
continue to have biased and judgmental attitudes toward religious clients, and often, they
pathologize clients’ spirituality and religious beliefs (Crosby & Bossley, 2012; Stetz et
al., 2011). Counselors need to increase their effectiveness in addressing clients’ spiritual
issues. Developing these competencies is necessary to adhere to the American
Counseling Association’s (ACA; 2014) professional standards that urge respect for
diversity and nondiscriminatory attitudes toward clients’ religious beliefs.
Henriksen et al. (2015) conducted a phenomenological study of counseling
students’ views on their preparedness to discuss religious and spiritual issues in
counseling. They found that 50% of the 113 students who participated in the study
indicated that their programs did not sufficiently address the necessity to be sensitive to
clients’ religiosity and beliefs. Like Henriksen et al., Adams (2012) reported that two

thirds of 118 counseling students indicated their reluctance to incorporate clients’
religious beliefs as an integral aspect of counseling. Together, these two studies
underscore the need for counselor educators’ continued efforts to train future counselors
to develop competencies in this domain and increase their comfort in working with
religious clients. For instance, counselor educators can improve students’ readiness by
teaching counseling students the contribution of spiritual beliefs and religious practices to
human development (Colbert et al., 2009; Crosby & Bossley, 2012; Henriksen et al.,
2015).
To this end, the findings from the current study can be valuable. First, the results
can help counselors and counselor educators understand Evangelical Christians’ mental
health experiences and needs adequately. Secondly, the results can increase counselors’
effectiveness by better understanding the cultural aspects of religion and its value in
Evangelical clients’ lives (see Crosby & Bossley, 2012). Lastly, individuals who
participated in this study used it as an opportunity to share their stories of genuine human
experiences. As mental distress remains a taboo topic (Neely-Fairbanks et al., 2018;
Smietana, 2014), stories about mental health conditions from the perspectives of those
living close to them can enrich conversations about mental distress. These stories can
change how church leaders and congregants engage mental distress challenges in
Evangelical faith communities (see Rogers et al., 2012; Vacek, 2015).
In this chapter, I present information to give context to this study involving
Evangelical Christians’ daily living experiences with a family member’s mental health

challenges. Next, I define the research problem addressed in this study and explain its
purpose and theoretical foundation. After proposing the definitions of key terms in the
study, I clarify my assumptions and discuss the study’s delimitations and limitations.
Then, I elaborate on the study’s significance, highlighting its potential contribution to
improving counselors’ effectiveness in working with religious clients. The chapter ends
with a summary of the main points covered.
Background
Mental health challenges within Evangelical faith communities are multifaceted,
characterized by diverse beliefs about mental distress causes and treatment approaches.
The explanations for mental distress include biological factors (Payne & Hays, 2016;
Stanford & Philpott, 2011), adverse psychological conditions (Santos & Kalibatseva,
2019; Trice & Bjorck, 2006), and spiritual causes (Avent et al., 2015; Payne & Hays,
2016). There is often a relationship between people’s religious beliefs, views about
mental distress, and attitudes towards people living with mental distress (Stanford, 2007;
Wesselmann et al., 2015). For example, Freeman and Baldwin (2020) studied the role of
religious beliefs in individuals’ attitudes about mental distress, its causes, and treatments.
Participants who attributed religious causes to mental distress were more likely to
endorse religiously based treatment options. Moreover, the participants held stigmatizing
views about mental distress and showed inadequate mental health literacy (Freeman &
Baldwin, 2020).

Freeman and Baldwin’s (2020) findings corroborated Jones et al.’s (2012) study
results. Jones et al. found that pastors who considered mental distress the product of a
person’s spiritual experiences preferred spiritual treatment approaches. Adams et al.
(2018) studied U.S. Christian college students to understand the connection between their
religious beliefs and attitudes toward people living with mental distress. They found that,
compared to Christians in general, fundamentalists endorsed more stigmatizing beliefs
and attitudes about mental distress; hence, the more conservative a person’s religious
beliefs, the more stigmatizing their attitudes may be toward other people’s mental distress
experiences.
Christians in Evangelical Faith communities struggle with mental health
challenges like many people in the U.S. general population (National Institute of Mental
Health, 2017; Rogers et al., 2012; Smietana, 2014). For instance, they confront several
challenges ranging from stigma to lack of adequate social support in their faith
communities (Freeman & Baldwin, 2020; Rogers et al., 2012; Wesselmann & Graziano,
2010). After an extensive review of the current literature, I have found only one
quantitative research study by Rogers et al. (2012) that focused on the effects of mental
distress on Evangelical family members in the context of their faith communities. Rogers
et al. noted that families living with mental distress experienced more stressors, increased
financial difficulties, and frequent conflictual interactions than families without mental
distress. Additionally, family members expressed how mental distress in the family
negatively affected their faith practices and relationships within the faith community.

Rogers et al. (2012) highlighted ambivalent and complex dynamics in the
relationships between Christians living with a family member experiencing mental health
challenges and their faith communities. However, the authors did not explore
participants’ daily struggles living with a family member who experienced mental
distress. Their study could not yield relevant details about participants’ daily lives to
increase the understanding of their mental health needs and inform how church leaders
and counselors could support them.
An in-depth study of Evangelical Christians’ daily experiences living with a
family member who suffered mental health challenges can yield findings to enrich
counselors’ understanding of the unique needs and challenges facing individuals in this
U.S. subculture. When families living with mental distress participate in counseling, they
experience greater family cohesion and functioning (Wang et al., 2019). In counseling,
family members can also access appropriate information about mental distress, which
empowers them and reduces their mental distress stigma experiences (Barr et al., 2020).
Lastly, the findings from the current study can increase the mental health literacy of
counselors and church leaders and have a positive impact on how they address the mental
needs of individuals who seek their support or services (see Jorm, 2000; Sanden et al.,
2015; Vermaas et al., 2017).
Problem Statement
Mental disorders refer to health conditions that adversely affect people’s thinking,
emotion, and behavior, with significant disturbances in their ability to be productive at

work, relate to others, and engage in family activities (American Psychiatric Association
[APA], 2020; National Alliance on Mental Illness [NAMI], 2020). In 2018, 1 in 5 adults
and 1 in 6 youth in the United States experienced mental disorders (NAMI, 2020). The
debilitating impact of a person’s mental health challenges often extends to their family
members with financial burdens, mental and physical exhaustion, and emotional
problems detrimental to their well-being (Eaton et al., 2016; Fekadu et al., 2019;
Liegghio, 2017; NAMI, 2020; Rogers et al., 2012).
Mental distress affects about 1 in 3 Evangelical Christian families in faith
congregations (Rogers et al., 2012). Those living with the mental distress of a family
member confront stigmatizing views in their faith communities, suggesting that a mental
disorder is a sign of spiritual weakness and personal failures rather than a treatable mental
health condition (McGuire & Pace, 2018; Peteet, 2019; Rogers et al., 2012; Stanford,
2007; Vacek, 2015; Wesselmann et al., 2015; Wesselmann & Graziano, 2010). While
Christians living with a family member experiencing mental distress prefer and seek
support from within their faith communities, fellow congregants and church leaders are
often either unaware of their daily struggles or underappreciate their concerns (Rogers et
al., 2012; Smietana, 2014; Stanford & McAlister, 2008; Stetz et al., 2011; Wong et al.,
2018). Such apathy and lack of engagement with these families’ plight leave them more
vulnerable, facilitating their suffering and isolation (Rogers et al., 2012).
Furthermore, Evangelical Christians tend to underutilize professional counseling
services, relying on their spiritual practices and preferring support within their faith
communities (Rogers et al., 2012; Royal & Thompson, 2012; Salwen et al., 2017).

Accrediting bodies such as the Council for Accreditation of Counseling and Related
Educational Programs (2016) require that students in Council for Accreditation of
Counseling and Related Educational Programs-accredited counseling programs train to
recognize the influence of clients’ spiritual beliefs on the counseling process. There is
also an expectation for mental health counselors to develop competencies to address
clients’ spiritual issues (ACA, 2014). Nonetheless, professional counselors continue to
struggle to attend to clients’ spiritual needs due to inadequate training (Curry et al., 2015;
Oxhandler et al., 2019). Counselors’ discomfort about clients’ spiritual issues is also an
obstacle to meeting religious clients’ needs (Curry et al., 2015; Oxhandler et al., 2019).
Evangelical Christians have historically been distrustful of mental health
counselors for their professional ethics and practices deemed incompatible with
Evangelical Christian religious beliefs (Cragun & Friedlander, 2012; Harris et al., 2016;
Royal & Thompson, 2012; Sullivan et al., 2014; Vacek, 2015). The lack of preparedness
of professional mental health counselors to work with clients with religious beliefs,
coupled with Evangelical Christians’ distrust of the professional mental health
community, deters the latter from seeking professional help (Bohecker et al., 2017;
Cragun & Friedlander, 2012; Curry et al., 2015; Harris et al., 2016; Oxhandler et al.,
2017). Unable to find support within their faith communities and less likely to seek and
benefit from professional mental health services, Evangelical Christians living with a
family member experiencing mental distress are at an increased risk of experiencing
additional stressors.

This study filled a gap in the literature by describing Evangelical Christians’ daily
experiences living with a family member who suffered mental health challenges. This
qualitative study exploring Evangelical Christian families’ experiences yielded invaluable
firsthand accounts to increase counselors’ understanding of the specific needs and
challenges confronting this diverse population. An increased understanding of this
population’s mental health challenges can enhance the quality of the mental health
support services for them. Counselor educators may also use such information to train
future counselors and foster their readiness to work competently with Evangelical
clients.
Purpose of the Study
The purpose of this descriptive phenomenological study was to explore and
describe Evangelical Christians’ everyday life with a family member who experienced
mental distress. I used in-depth interviews to facilitate the description of participants’
experiences through the lens of their religious beliefs and membership in a faith
community. Specifically, I explored participants’ attitudes and views of mental distress,
their sense of self and the family member experiencing mental distress, and how they
made meaning of their overall experiences. Such a focus on participants’ experiences
yielded relevant information for counselors to use to work more efficiently with clients
from this culturally diverse population. The results can also inform counselor educators in
training future counselors. Finally, findings from this study can raise church leaders’

awareness of the issue and support their ministries to address the daily needs of
congregants living with a family member who is experiencing mental distress.
Research Questions
The following research question and subquestions guided this study:
Research Question: How do Evangelical Christians describe their day-to-day life
with a family member experiencing mental distress?
Subquestion 1: How do Evangelical Christians living with a family
member experiencing mental health conditions view mental distress?
Subquestion 2: What are Evangelical Christians’ perceptions of their faith
community’s responses to their day-to-day life with a family member
experiencing mental distress?
Theoretical Foundation
I used transcendental (or descriptive) phenomenology as the theoretical
framework to explore Evangelical Christians’ day-to-day life with a member
experiencing mental health challenges. The philosophical work of Edmund Husserl
(2017), which is foundational to descriptive phenomenology, emphasizes the discovery of
knowledge through understanding the nature or essence of a phenomenon and not its
facts. Phenomenology, therefore, becomes a means of describing how a phenomenon
presents itself to a person’s consciousness. Husserl posited that consciousness is the
medium for discovering knowledge, which begins with human experience.

The use of descriptive phenomenology requires an understanding of several
concepts, including intentionality. Intentionality is an essential quality of consciousness
to be always about something (Belousov, 2016; Moran & Cohen, 2012). Integral to
intentionality are noesis and noema, two components associated with conscious
experiences. Noesis represents the process of experiencing, the intentional mental
process, which is necessary to make sense of an experience as it appears to consciousness
(Cerbone, 2014; Moran & Cohen, 2012). Noema refers to the intentional object that is
perceived or the content experienced. Any description of consciousness is dependent on
noema (Cerbone, 2014; Moran & Cohen, 2012). In Husserl’s philosophy, noesis and
noema work in conjunction, giving researchers access to another person’s consciousness
and aspects of the experience they are interested in describing (Giorgi, 2009).
Researchers using descriptive phenomenology must assume a phenomenological
reduction attitude to explore participants’ experiences. Phenomenological reduction refers
to the researcher’s posture toward understanding the phenomenon as it presents itself to
participants’ consciousness, namely, how they perceive and experience it (Giorgi, 2009).
An effective phenomenological reduction requires the practice of epoché or bracketing.
Epoché consists of the researcher withholding their views and assumptions related to the
phenomenon under study because doing so allows them to gain full access to participants’
experiences without interference (Cerbone, 2014; Giorgi, 2009; Husserl, 2017).
Bracketing enables the researchers to direct their attention to the experiences under
exploration. Ultimately, the researcher’s goal is to describe what participants report about

their experiences without interpreting or offering additional explanations (Giorgi, 2008,
2009).
The descriptive phenomenological approach enabled me to explore and describe
participants’ day-to-day experiences living with another person experiencing mental
distress. Participants shared their experiences of mental distress as presented to their
consciousness. My goal was to maintain fidelity to participants’ experiences.
Accordingly, phenomenology was a uniquely suitable method to provide the framework
with which to explore the nature of participants’ experiences living with a family member
who suffered mental distress. It allowed me to follow a systematic process while
accessing and describing participants’ experiential world, how they lived, addressed
challenges, and made sense of their circumstances (see Giorgi, 2009, 2012).
Nature of the Study
The purpose of this descriptive phenomenological study was to explore and
describe Evangelical Christians’ everyday life with a family member who experienced
mental distress. Conducting the qualitative research study through a phenomenological
lens revealed the depth and complexity of living with another person experiencing mental
distress from the participants’ perspectives (see Qutoshi, 2018). Knowledge obtained
from this study will increase the familiarity of counselors and counselor educators with
Evangelical Christians’ perceptions of themselves, their attitudes, and their needs living
with another person’s mental distress. Additionally, future counselors can use the
findings from this study to improve their effectiveness in working with religious clients.

I recruited eight adults who self-identified as Evangelical Christians to participate
in the study. Prospective participants were family members of individuals with mental
distress. After collecting data through semistructured interviews, I analyzed the data
using Giorgi’s (2009, 2012) descriptive phenomenological method to explore and
describe the research participants’ experiences.
Definitions
Clergy members: Individuals with a sense of divine or vocational calling to serve
God and their faith community. They have often received spiritual formation and
theological training to teach the Bible as well as comfort and assist congregants in need
(Joynt, 2017; Krause et al., 1998).
Evangelical Christians: Religious people who share specific beliefs within
Christianity. First, Evangelical Christians believe in the Bible as the inspired word of
God, the highest authority that ascertains Christians’ beliefs, moral conduct, and spiritual
practices. Secondly, Evangelical Christians believe in the biblical personage, Jesus
Christ, as the Son of God. For Evangelicals, Jesus’ death on the cross is of utmost
significance and is the ultimate means for God to forgive a person whose life conduct
falls short of God’s moral expectations. Thirdly, Evangelical Christians believe that the
only way to be in the right relationship with God is for individuals to renounce their
former ways of life, trust, and accept Jesus Christ as their Savior. Lastly, Evangelical
Christians believe in sharing their faith with other people to bring them to believe and
follow Jesus Christ (Bebbington, 1989; Caffrey, 2018; National Association of
Evangelicals, n.d.; Thurston & Seegobin, 2014).

Faith community: A community of people who gather in a specific geographical
location to worship. In this community, worshippers or congregants are united in their
quest to know God. They interact with one another, participate in shared religious
activities, and develop a sense of solidarity within intimate and caring relationships
(Dinham, 2011).
Family and family members: I opted for the structural definition, which also
represents the traditional conception of family. As such, a family comprises at least two
people who share a household and are related by birth, marriage, or adoption. In the
family, individuals form relationships, interact with one another, and form an emotional
unit (Kerr & Bowen, 1988; Segrin & Flora, 2004; U.S. Census Bureau, 2020).
Mental distress: The different mental health conditions that cause suffering and
impairment in a person’s cognitive, emotional, and behavioral functioning (APA, 2013). I
purposefully use the term mental distress instead of mental illness or mental disorder to
move away from the medical model or expert knowledge about mental health conditions;
instead, I want to emphasize participants’ concrete experiences of how mental distress
touches their lives daily (see Borg et al., 2009). Throughout this study, mental distress
represents any mental health condition, regardless of its severity, including anxiety
disorder, major depression, schizophrenia, or bipolar disorder, that disrupts a person’s
well-functioning and prevents them from living a productive life.
Self-stigma: The public, biased, and stereotypical beliefs about people with mental
distress that individuals internalize and apply to themselves. Self-stigma can cause

selfshame, decrease self-esteem, and lead to social inadequacy. Self-stigmatized
individuals also experienced self-blame for their and other peoples’ mental distress
experiences (Corrigan et al., 2016; Eaton et al., 2016; Lucksted & Drapalski, 2015;
Tucker et al., 2013).
Stigma: An attribute or feature that marks an individual as odd. In other people’s
views, that feature degrades a person’s identity. Such a feature exposes the individual to
contempt in their community, disrupting their well-being and functioning (Bos et al.,
2013; Goffman, 1963).
Assumptions
In agreeing to participate in this descriptive phenomenological study, I assumed
that respondents intended to share their stories and contribute to my research.
Furthermore, I assumed that participants’ descriptions of their experiences living with a
family member who suffered mental distress, while based on their perceptions of their
circumstances, would be authentic and accurate accounts of the phenomenon under study.
Therefore, I anticipated that prospective participants would volunteer to share
information about their experiences living with a family member with mental distress
truthfully. Given the stigma about mental distress in Evangelical faith communities and
the general population, I speculated that some prospective participants might be living
with self-stigma and distrust my intentions. I assumed that spending the necessary time
building a trusting relationship with participants and maintaining a nonjudgmental
attitude would facilitate their self-disclosure.

Scope and Delimitations
Although mental health experiences are ever-present in all communities in the
United States, I centered this study on Evangelical faith communities. Specifically, I
focused on Christians’ experiences of living with a family member with mental distress.
Many families confronting a family member’s mental distress often receive limited social
support in their Evangelical faith communities (Rogers et al., 2012; Stanford, 2007). The
current study yielded findings that can enhance the understanding of counselors and faith
leaders of these family members’ unique challenges. The self-disclosing of mental
distress accounts from family members can increase awareness of mental distress needs
within faith communities and foster positive changes that benefit others (see Rogers et al.,
2012).
I interviewed participants who have or had family members with mental distress.
Participants subscribed to Evangelical faith tenets, as I defined in this study.
Additionally, participants were active members of their faith and faith community (i.e.,
attending church functions regularly). Participants were also parents, spouses, or siblings
of the family member living with mental distress when the study took place. In other
words, their experiences were long-standing.
I recruited participants throughout the United States, regardless of their gender or
racial backgrounds, so long as they met the inclusion criteria for participation in the
study. Excluded from participation in this study were: (a) family members with diagnosed
mental distress and (b) individuals under 18 years old. I recruited eight participants and

determined my final sample size after reaching data saturation. Potential participants
were screened for their eligibility to contribute to the study before being interviewed (see
Appendix B).
In this study, I broadened my research scope to include all mental distress types,
regardless of their severity; consequently, participants’ experiences were not limited to
any single type of mental distress. By focusing on lived experiences, I attempted to
highlight invariant features in participants’ accounts of their experiences of another
person’s mental distress. Furthermore, as I incorporated enough detail about the study’s
context and descriptions of participants’ experiences, readers can relate to one or more
characteristics of the phenomenon under study, thus increasing the transferability of the
study’s findings (see Cope, 2014; Shenton, 2004).
Limitations
First, the presence of mental distress stigma within Evangelical faith communities
was a potential obstacle to recruiting participants with experiences of the phenomenon I
planned to explore. Second, the interviewer-interviewee relationship dynamics during the
interview process and poorly designed questions could have impeded the in-depth
descriptions of participants’ experiences. However, I developed a good rapport with the
participants through showing a genuine interest in their lives throughout my interactions
with them, from recruitment to interviewing. I attended to their legitimate concerns about
their well-being and ensured they understood the purpose, benefits, and potential risks of
participating in the study. In the interviews, I asked well-constructed questions that were

appropriate to address the research questions. Before the interviews took place, my
dissertation committee members evaluated the interview questions to ensure that I
respected participants’ rights and dignity and showed sensitivity to their experiences. A
third limitation involved the sample size for this phenomenological study. I used a
purposive sample of eight participants; however, I determined my final sample size only
after reaching data saturation. Therefore, any transferability of the study findings would
be relevant only to the population that reflects the characteristics represented in the
study’s sample (Battaglia, 2008; Daniel, 2012). A fourth limiting condition involved my
role as an observer participant in the study who conducted the interviews and collected
and analyzed the resulting data. My professional and personal preunderstanding of the
phenomenon under exploration inevitably influenced my reporting of the study findings.
By bracketing and adopting a rigorous and proven data analysis method, Giorgi’s (2009)
descriptive phenomenological psychological method, and following its structured
procedures to analyze the data and report findings, I avoided injecting my biases into the
study (see Shelton & Bridges, 2019).
Significance
Like many individuals in the general U.S. population, Evangelical Christians in
faith communities experience mental distress and their resulting life-debilitating effects
(Rogers et al., 2012; Sullivan et al., 2014). A quarter of adults (n = 61 million) in the
United States self-identified as Evangelical Christians (Pew Research Center, 2015). Yet,
there is little information in the scholarly literature about their perspectives on mental

distress and day-to-day mental health challenges. Increased familiarity with Evangelical
Christians’ experiences living with family members’ mental health challenges can
enhance counselors’ effectiveness in working with this significant segment of the U.S.
population. The findings of this study can inform counselors’ practice and increase their
awareness of the unique challenges and mental health needs confronting this diverse
group of people. For example, mental health counselors can use the findings to help
facilitate a counseling process that is culturally relevant to religious clients (see ACA,
2014). The findings can also further the dialogue toward integrating Christian worldviews
into counseling programs. Doing so can ensure that future counselors develop
competencies to work with clients who prefer spiritually focused counseling. Finally, I
hope that participants who shared their stories in this study will step forward to do the
same in their faith communities. Their decision to speak about their mental health
experiences can encourage others in similar situations to voice their concerns and
advocate for their needs in their communities.
Summary
Individuals with mental distress in their families are often invisible to fellow
congregants and clergy members often seem unprepared to assist these families, leaving
family members alone in their struggles, lacking support and resources to meet their
mental health needs (Jones et al., 2012; Rogers et al., 2012; Wong et al., 2018). Informed
knowledge about these families’ mental health experiences from their perspectives could
help break the silence and stigma about mental distress in faith communities.

Additionally, family members’ accounts can increase counselors’ understanding of the
mental health needs of individuals living with another person’s mental distress. In this
chapter, I introduced my dissertation topic and provided a rationale for conducting the
study. In the following chapter, I will present a summary and synthesis of current
knowledge about mental distress in Evangelical faith communities. The literature search
strategies for finding relevant information and the theoretical foundation and research
method of the study will also be discussed.
Chapter 2: Literature Review
In many communities in the United States, including faith communities,
individuals and families confront mental distress and its devastating effects, such as
stress, stigma, and mental health problems (Avent et al., 2015; Fekadu et al., 2019;
National Institute of Mental Health, 2017; Rogers et al., 2012). Mental distress in the
family affects all members, extending even to the broader community in which the
concerned individuals live (Eaton et al., 2016; Fekadu et al., 2019; Liegghio, 2017;
Rogers et al., 2012). Family members’ physical and emotional proximity to a person
experiencing mental distress can expose them to immense physical, emotional, and
financial difficulties that threaten their well-being (Fekadu et al., 2019; Lin et al., 2018;
Rodríguez-Meirinhos et al., 2018).
There is a growing recognition of mental distress in Christian faith communities
(Kinghorn, 2016). Increasingly, clergy members have reported widespread contact with
congregants’ mental distress experiences (Anthony et al., 2015; Hunter & Stanford, 2014;

Stanford & Philpott, 2011). Clergy members are also involved in providing counseling as
an integral part of their ministry to assist individuals living with mental distress in faith
communities (Anthony et al., 2015; Hedman, 2014).
Faith communities are the preferred places for Christian families living with
mental distress to seek help; however, families and individuals who expect support and
mental health resources from their faith communities often encounter several obstacles
(Jang et al., 2017; Rogers et al., 2012). For example, fellow congregants seemed unaware
of the mental health concerns of other members in their faith community, and they were
more likely to empathize with physical ailments than a person’s mental health conditions
(Payne & Hays, 2016; Rogers et al., 2012). Additionally, church leaders reported
inadequacies in their mental health literacy and resources to meet the mental health needs
in their faith communities (Anthony et al., 2015; Jang et al., 2017; Payne & Hays, 2016;
Rogers et al., 2012; Wong et al., 2018). Lastly, families and individuals experiencing
mental distress have reported unpleasant experiences within their faith communities due
to mental distress stigma (Baker & Procter, 2015; Rogers et al., 2012; Stanford, 2007).
They also encountered the loss of friendships that increased their isolation (Baker &
Procter, 2015; Rogers et al., 2012; Stanford, 2007).
Many Evangelical Christians living with mental distress reported distrust of
professional mental health counseling, considering its ethics and practices incompatible
with their religious faith (Harris et al., 2016; Royal & Thompson, 2012; Sullivan et al.,
2014). Some professional counselors may lack appreciation for their clients’ religious

convictions, undervaluing religion and religious leaders’ contributions to treating mental
distress; consequently, Evangelical Christians were often reluctant to seek professional
support for their mental health needs (Cragun & Friedlander, 2012; Harris et al., 2016;
Royal & Thompson, 2012; Sullivan et al., 2014). Moreover, an examination of the
literature regarding mental health professionals’ readiness to incorporate religion and
spirituality in counseling suggested that many counselors lack training and are uneasy
about working with religious clients (Curry et al., 2015; Oxhandler et al., 2019). Without
adequate support, Evangelical Christians living with a family member experiencing
mental distress may continue to live with unmet mental health needs; consequently, they
are at an increased risk of experiencing additional stressors (see Bledsoe et al., 2013;
Fekadu et al., 2019).
Numerous studies have explored the beliefs and attitudes about mental distress,
the effects of mental distress, and mental health programming in Evangelical faith
communities (Anthony et al., 2015; Csiernik et al., 2020; Rogers et al., 2012; Santos &
Kalibatseva, 2019; Sullivan et al., 2014). However, little is known about Evangelical
Christians’ day-to-day realities of living with a family member experiencing mental
distress. Providing adequate support services to this portion of the U.S. population may
require a better understanding of their challenges. Rogers et al. (2012) asserted that
stories of Evangelical families living with mental distress would benefit others in similar
circumstances. Congregants could find encouragement in hearing about families’
experiences of living with a member’s mental distress. Such mental health accounts could

also inform clergy members’ efforts to provide adequate support services to families
living with mental distress (see Rogers et al., 2012).
Thus, the purpose of this study was to explore and describe Evangelical
Christians’ everyday life with a family member experiencing mental distress through the
lens of their religious beliefs and involvement in faith communities. The more mental
health professionals and other service providers recognize and learn from Christian
families’ lived experiences of mental distress, the more prepared they may be to help
undiagnosed family members meet their mental health needs.
In Chapter 2, I explain the search strategies used to find pertinent information in
the extant literature on mental distress in Evangelical faith communities. Then, the
conceptual framework is discussed, providing a rationale for the choice of research
method. Finally, I review the current literature on the mental distress experiences of
Evangelical Christians, including the history between religion and mental distress with a
poignant reflection of the contentious relationship between religion and science in
shaping the understanding of mental distress. After reviewing the effects of mental
distress on family functioning and discussing the mental distress experiences in
Evangelical Christian families in faith communities, Chapter 2 concludes with a review
of selected phenomenological studies.
Literature Search Strategies
I conducted a Boolean search that allowed me to combine my key search words
using Boolean operators such as “AND” or “OR” to expand or narrow my searches for

accurate results. I excluded editorials and book reviews from my search and focused on
peer-reviewed articles. Three successive steps were followed. First, I searched five
databases and one search engine (i.e., PsycInfo, PsycArticles, Medline with Full Text,
SAGE Journals, SocINDEX with Full Text, and Google Scholar) using various
combinations of my preselected key search terms to enhance my search results. The
keywords searched were mental health, mental illness, mental disorder or psychiatric
illness; mental illness in the church; Protestants, Baptists, Evangelical Christians, or
Fundamental Christians; faith community or church community; attribution, beliefs,
attitudes, perception or stigma; the impact of mental illness; family members or relatives
or next of kin or family; pastors, or church leaders; congregants or church members; and
coping strategies or coping skills or coping or cope. While limiting my search to
peerreviewed articles, I searched the databases from their establishment to the present
day, not limiting my inquiries by date. I proceeded that way because I wanted to locate as
many articles as possible that provided critical findings and historical perspectives for my
study. As a result, a few of the publications I consulted are quite dated; nonetheless, they
represented the available literature I could find on the topic.
Secondly, I snowball searched, using the reference list of one article to find
additional relevant literature. My search was broadened to include all mental distress
types, irrespective of their severity. Finally, I read articles’ titles and screened abstracts
for their potential relevance to my dissertation. Then, I arranged the selected articles of

interest by topics, reread them thoroughly to grasp their content, and used the relevant
information gathered to support my research.
Theoretical Foundation
I selected transcendental phenomenology as the research design to study
Evangelical Christians’ first-person accounts of their everyday realities living with a
family member experiencing mental distress. As a philosophy, phenomenology purports
that consciousness is the doorway to any knowledge, and any claim to knowledge begins
with experience because human beings interact with the world and engage in daily
experiences through their consciousness (Giorgi, 2009, 2012; Husserl, 2017), Moustakas
(1994) suggested that phenomenology was the primary mode of obtaining knowledge. As
a research method, phenomenology offers researchers a systematic approach to
understanding and describing a phenomenon of interest (Moustakas, 1994). Giorgi (2009,
2012) asserted that access to knowledge passes through understanding how people
approach daily experiences and make sense of them. As such, researchers can gain
knowledge by exploring human experiences from participants’ viewpoints or
consciousness.
Researchers interested in conducting phenomenological studies can choose from
two main approaches. The first phenomenological approach, transcendental
phenomenology, represents Husserl’s philosophy. Husserl’s (2017) phenomenology is
essentially descriptive and the “court of appeal for the fundamental questions of
psychological methodology,” allowing researchers to identify and describe the

psychological essence and structure of the phenomenon of interest in participants’
experiences (p. 231). Hence, transcendental phenomenology is a tool for understanding
human experiences. According to Giorgi and Giorgi (2003) and Giorgi (2012),
transcendental phenomenology neither imposes meaning on participants’ stories nor
shapes their experiences; consequently, transcendental phenomenologists seek to
understand and describe human experiences from participants’ perspectives (Giorgi,
2012; Giorgi & Giorgi, 2003). Additionally, transcendental phenomenology researchers
do not attempt to conceptualize or derive theoretical principles from participants’
accounts of their experiences to explain the phenomenon; instead, the goal is to describe
the fundamental meanings or structures of experiences (Gee et al., 2013). The
second approach represents Heidegger’s philosophy; Heidegger’s phenomenology is
hermeneutic and interpretive (Cerbone, 2014). Researchers adhering to Heideggerian
phenomenology believe that interpreting is integral to living and is essential for making
sense of daily lived experiences; therefore, they suggest that describing participants’
experiences is to interpret them. Interpretation is fundamental to doing hermeneutic
phenomenology (Zahavi, 2019). Contrary to researchers’ position in hermeneutic
phenomenology, descriptive phenomenologists accept participants’ experiences as
shared, and they neither enhance nor remove anything from participants’ descriptions of
their lived experiences (Giorgi, 2012).
A key concept in phenomenology is intuition. Intuition is Husserl’s term to refer
to how an object or phenomenon appears to consciousness (Finlay, 2011). Researchers

have intuition into a phenomenon when they can see or grasp its essential structures as
presented to their consciousness (Finlay, 2011; Moran & Cohen, 2012). According to
Husserl (2017), phenomenologists do not rely on hypotheses or theories to understand a
phenomenon; instead, they accept how the phenomenon presents itself to their
consciousness as legitimate knowledge.
Another fundamental concept in transcendental phenomenology is intentionality.
Intentionality is the property of consciousness to maintain constant awareness, and it
refers to an individual’s capability to maintain or direct their attention toward something
(Belousov, 2016; Moran & Cohen, 2012). To that extent, Giorgi (1999) concluded that
the essence of consciousness is intentionality because conscious activities are intentional,
ultimately directed at objects or experiences. While bracketing may be a complex
technique to implement (Giorgi, 2009), my ability as a researcher to focus and direct my
attention to participants’ accounts is essential to being present and listening intently to
their experiences of living with someone else’s mental distress.
Transcendental phenomenology offers researchers a rigorous approach to
exploring human experiences through phenomenological reduction. The goal of using
phenomenological reduction is to transcend the natural attitude of consciousness (which
often posits reality as already being there) to apprehend the phenomenon under study
(Giorgi, 2008, 2009; Moran & Cohen, 2012). According to Husserl (2017),
phenomenological reduction is a prerequisite to using the phenomenological method;
thus, researchers must view participants’ experiences from the perspective of

consciousness (i.e., how they experienced the phenomenon; Giorgi, 2009; Moran &
Cohen, 2012).
Giorgi (2008) suggested that researchers first practice epoché, which entails
withholding or suspending previous insights and knowledge about the phenomenon under
study to assume the phenomenological reduction. Epoché is not a denial of past
experiences but an openness to appreciate the phenomenon under study afresh. It is an
unencumbered way of looking at a phenomenon or reality, allowing the researchers to
capture what the phenomenon reveals about itself to their consciousness (Moran &
Cohen, 2012; Moustakas, 1994).
Transcendental phenomenologists use bracketing to implement phenomenological
reduction. Bracketing consists of a shift in attitude, allowing the researcher to engage the
ongoing experience as wholly as possible (Giorgi, 2008, 2009). Bracketing increases the
researchers’ attentiveness to be present to experiences by adopting a rigorous attitude that
allows them to recognize and describe the variances between their past knowledge of the
phenomenon and the new knowledge emanating from participants’ experiences (Giorgi,
2008, 2009). Rolls and Relf (2006) suggested that qualitative researchers would benefit
from participating in bracketing interviews to increase awareness of their past
experiences and process assumptions that could interfere with listening intentionally to
participants’ stories.
Several researchers have used phenomenology as a research design to explore
families’ experiences living with mental distress (Chang & Horrocks, 2006; Eaton et al.,

2016; Milbourn et al., 2015; Shamsaei et al., 2015). Chang and Horrocks (2006) used
hermeneutic phenomenology to explore the meaning-making processes of individuals
caring for relatives with mental distress. Shamsaei et al. (2015) used Colaizzi’s
phenomenological method to study caregivers’ challenges with family members’ mental
distress. Eaton et al. (2016) applied transcendental phenomenology to explore families’
mental distress experiences. Using Giorgi’s descriptive phenomenological method to
explore self-stigma experiences in parents of children with emotional and behavioral
disorders, Eaton et al. successfully identified themes that captured the essence of parental
experiences with self-stigma and concluded that self-stigma had detrimental effects on
participants’ well-functioning. Similarly, Meadus and Johnson (2000) described
adolescents’ experiences living with their parents’ mood disorders. The researchers
employed Giorgi’s phenomenological method to analyze their data, which allowed them
to focus on the uniqueness of each participant’s story and still discover the essential
structures of their experiences.
The merit of a phenomenological study is that it can help researchers uncover
research participants’ perspectives of the phenomenon under study instead of an expert’s
or professional knowledge about it (Borg et al., 2009). Giorgi’s (2009) descriptive
phenomenological psychological method was an appropriate framework to analyze and
describe the psychological essence and structure of how Evangelical Christians live with
their family members’ mental distress. As Giorgi (2002) insisted, fidelity to the
phenomenon is paramount in phenomenology; therefore, I refrained from imposing my

views and interpretations on participants’ experiences and instead the study findings
reflected the participants’ experiences (see Giorgi & Giorgi, 2003). I focused on
obtaining detailed descriptions of participants’ accounts to thoroughly understand the
phenomenon as they experienced and expressed it (see Qutoshi, 2018).
Literature Review
In this section, I present a brief history of mental distress within U.S. Christianity.
It is a history that parallels an often-fraught relationship between religion and psychiatry,
two influential social entities with shared, but sometimes opposing, systems of ethics,
values, and practices (Every-Palmer et al., 2020; Moreira-Almeida et al., 2016; Southard
et al., 2020). I start with a review of mental distress in the church in the 18th century
United States. Afterward, the relationship between religion, psychiatry, and counseling is
briefly discussed and the beliefs and attitudes about mental distress throughout church
history are examined. I conclude with a presentation about the church’s engagement with
individuals experiencing mental distress and their families.
Religion and Mental Health
Religion remains a source of strength, hope, and purpose to billions of people in
modern-day societies (Bonelli & Koenig, 2013; Garssen et al., 2020; Koenig, 2009;
Torrecillas et al., 2020). Many researchers interested in understanding the connection
between religion and mental health undertook various studies across multiple religions
with conclusive evidence about its positive contributions to well-being. For instance,
Mahjoob et al. (2016) found that listening to a voice recitation of Quran verses had a

calming effect on listeners, while Pajević et al. (2017) showed the mental health benefits
of daily Quranic prayers in reducing risks for impulsiveness and aggression in Bosniac
war veterans. Furthermore, observance of the Islamic codes of conduct promoted social
welfare and mental health, regulating behaviors and interpersonal relationships (Baasher,
2001). Likewise, Jauncey and Strodl (2018) found that Christians who developed
meaningful and loving relationships with God and their fellow parishioners experienced
greater life satisfaction. Their well-being also improved as a result.
Every existing form of religion has costs and benefits for practicing individuals
(Pargament, 2002). To illustrate, Jocson et al. (2020) examined the effects of religion and
spirituality on Latino youth exposed to community violence. They found that religious
participation and spirituality had protective resources that supported the psychological
well-being of adolescents who experienced community violence. Conversely, Marks et al.
(2019) explored the religion-related struggles of religious minorities in the United States.
First, they found that religious minorities struggled with social acceptance in their
interactions with people outside their families and experienced discrimination and
exclusion. Secondly, these individuals reported dissatisfaction with religious teachings
and frustration with hypocritical faith leaders who violated their trust.
Religion and religious rituals have been essential to people’s daily functioning
throughout human history (Koenig, 2009, 2012). Religion is ubiquitous and will likely
remain a resource for people (see Pargament, 2002). While some individuals will
continue to face disappointing experiences with religion and faith institutions, many will

continue to embrace religion and find answers to their needs and reach their aspirations,
irrespective of their racial or cultural backgrounds (see Pargament, 2002).
Religion and Psychiatry: A History of Rivalry and Mutual Influence
Pargament and Lomax (2013) described the relationship between psychiatry and
religion as troubled. Despite their shared interests, which include a quest to understand
human experiences and behaviors and promote well-being and growth, the relationship
between psychiatry and religion was, at times, contemptuous, collaborative, and
competitive (Moreira-Almeida et al., 2016; Sullivan et al., 2014). Yet, practicing religion
has been synonymous with well-being because of its positive influence on people’s lives,
offering them stability and regulating social relationships with rules that promote
teamwork and mutual support (Koenig, 2009, 2012). For instance, the sacred texts for
Judaism and Christianity, which are more than 3,000 years old, contain dietary
restrictions, personal hygiene prescriptions, and moral codes to promote healthy
functioning (Moreira-Almeida et al., 2006). Also, religion was a social and psychological
medium fostering change and promoting mental wellness. It was influential in developing
humane treatment approaches to mental distress in the 19th century (Tanaquil, 1998).
Nonetheless, the emergence of medical and psychiatric treatment of mental
distress marked the beginning of a relationship of rivalry between religion in one camp
and psychiatry and psychology in the other camp (Koenig, 2009; Koenig & Larson, 2001;
Westerink, 2014). Prominent founders of psychiatry and psychology, such as the German

Emil Kraepelin (1856-1926) and the Austrian neurologist and father of psychoanalysis
Sigmund Freud (1856-1939), were critical of religion (Segal, 2010; Westerink, 2014).
Kraepelin believed that religion promoted mental distress, emphasizing sin, punishment,
and God’s judgment (Westerink, 2014). Likewise, Freud vehemently detested religion,
contending that it was dysfunctional, harmful, and deceptive (Segal, 2010). Apart from
claiming that religion has failed to protect and comfort individuals seeking refuge in it,
Freud also denigrated people’s religious experiences, suggesting that God was an illusion
(LaMothe, 2003). Even decades later, Freud’s views continued to influence many
practitioners and scholars who displayed negative attitudes toward religion, which they
viewed as childish and regressive (Pargament & Lomax, 2013).
However, psychologists such as William James (1842-1910) and Carl Jung
(18751961) favored including religion in the scientific discourse of their times. While
James believed that religion could add meaning to a person’s life and argued for the
scientific exploration and explanation of religion and religious experiences (Melo & de
Resende, 2020), Jung advocated for due consideration of religion in psychiatric practices
(Koenig & Larson, 2001). Jung believed religion was a natural function of human
psychology. Therefore, it was beneficial for those who embraced it (Melo & de Resende,
2020). Jung viewed religion as valuable for understanding the unconscious (Segal, 2010),
finding stability and peace within oneself, and as a tool for becoming whole (Pargament,
2002).

The effects of the antagonistic relationship between religion and psychiatry
expanded to the field of professional counseling as well. According to Harris et al.
(2016), professional mental health counselors have been dismissive of clients’ spiritual
practices and religious beliefs. These researchers evaluated the psychology research
literature on clients’ expectations regarding spiritual and religious issues in counseling.
They found that religious clients wanted to discuss their spiritual life in counseling;
however, they were afraid to do so because they perceived mental health counselors as
disposed to define religious beliefs or spiritual problems as deviant or harmful.
Clergy members also appeared suspicious of professional counselors. Openshaw
and Harr (2009) and Smith et al. (2018) found that clergy members were often aware of
their inability to adequately meet their congregants’ mental health needs. They
recognized the need for professional mental health to support their pastoral care
ministries; however, many clergy members reported mutual distrust between them and
mental health professionals. While some clergy members viewed counseling favorably,
they preferred to refer parishioners to the counselors deemed deferential and sympathetic
to their spiritual concerns.
Psychiatry and Christianity
Individuals within Christianity have also waged wars against psychiatry, labeling
it anti-God because its proponents dismissed faith and religious matters in their
conceptualization of human functioning (Kinghorn, 2016; Stanford, 2007; Sullivan et al.,
2014). Today, the sequelae of this rivalry characterize many Evangelical Christians’

attitudes vis-à-vis mental health issues. They can be observed in faith communities, as
well as in the suspicion with which people of faith and those in psychotherapeutic
communities view one another (Hodge et al., 2020; Stanford, 2007; Sullivan et al., 2014).
Clergy members have long been the expert voices regarding individuals’ mental
health concerns in ancient and contemporary communities. For clergy members, human
struggles were integral to their pastoral care. They were the healers of the body and mind;
however, with the advent of psychiatry and its acquired status as a professional and
secular discipline in the 18th century, physicians began to replace clergy members as
mental health services providers (Houston, 2004). As Houston concluded, the issue at
stake was the battle over which institution, religion, or psychiatry, can speak
authoritatively about human beings’ health and well-being. Or, as Sullivan et al. (2014)
put it more recently, clergy members saw in the medicalization of mental health a decline
of their influence and dismissal of faith as the solution to people’s emotional problems
and spiritual concerns.
Collaboration Between Psychiatry, Counseling, and Christianity
Despite the antagonism that characterized the relationship between religion and
psychiatry, Cohen (n.d.) and Verhagen (2017) suggested that collaboration and mutual
influence between both institutions were still possible. As is the case, a growing number
of scholars are promoting deference to people’s religious beliefs and incorporating
spiritual dimensions in the assessment and treatment of mental distress. Religion is a
coping resource for countless people worldwide; hence, integrating spirituality and

religious beliefs in treatment approaches to promote well-being is now acceptable. It is
even a recommended practice in psychiatry (Koenig, 2009; Moreira-Almeida et al., 2016;
Pargament & Lomax, 2013). Also, counseling organizations that promote counselors’
professional development support the inclusion of spirituality and religion in counseling
as standard practice for mental health counselors, regardless of their therapeutic
approaches (ACA, 2014).
Hartog and Gow (2005) observed that both adherents of Christianity and
psychiatry could be complementary, although their endorsed explanations of mental
distress’ causes and treatments may differ. There is ample evidence that many clergy
members throughout the history of the church and, particularly within U.S.
Evangelicalism, have integrated the biomedical explanations of mental distress into their
pastoral ministries (see Covey, 2005; Hodge et al., 2020; Houston, 2004; Jimenez, 1986;
Kinghorn, 2016; Stanford & Philpott, 2011).
However, the distrust toward psychology and psychiatry persists as many church
leaders still oppose psychology for its secular and humanistic foundation (see Hodge et
al., 2020; Mathews, 2008; Pargament & Lomax, 2013). Integration of psychology and
religion remains an uncomfortable compromise for some clergy members because they
believe their religious beliefs, which are foundational to their pastoral care ministries,
stand in opposition to the ethics governing the practice of psychology, psychiatry, and
counseling. They believe the values psychologists and psychiatrists endorse to be

incompatible with biblical teachings (see Hodge et al., 2020; Mathews, 2008; Pargament
& Lomax, 2013).
The conflicting relationship between Christianity and psychiatry is evident and
well-documented. While mental health counseling is a relatively newer discipline and
practice, in comparison to psychiatry, mental health counselors also have a history of
being dismissive of the role of religion and spirituality in mental health (Ellis, 1980;
Sullivan et al., 2014; Yamada et al., 2020). For example, so intense was Ellis’ (1980)
hostility toward religion that he regarded religious people as inflexible, bigoted, and
emotionally disturbed. For Ellis, the more religious people were, the more irrational they
acted with impaired mental and emotional functioning.
As a profession, mental health counseling has increasingly embraced religion and
spirituality in recent years (see ACA, 2014; Bohecker et al., 2017); however, many
mental health counselors continue to display a lack of respect for religion and their
clients’ religious beliefs (see Crosby & Bossley, 2012; Stetz et al., 2011). Also, some
counselors reported discomfort working with religious clients, often lacking the
competencies to integrate spiritual issues into counseling (see Curry et al., 2015;
Dobmeier & Reiner, 2012; Gladding & Crockett, 2019; Yamada et al., 2020).
Christian clergy members and mental health professionals may share many
common goals, including helping people discover their identity, live meaningfully, and
experience social support (Weisman de Mamani et al., 2010). However, church leaders
and congregants have also been skeptical of the values and practices that mental health

counselors endorsed (Bledsoe et al., 2013; Polson & Rogers, 2007; Smith et al., 2018).
Many clergy members consider collaboration with the mental health community a threat
to Christians, believing that such exposure will be detrimental to their congregants’
spiritual well-being (Baldwin & Poje, 2020; Hodge et al., 2020; Pargament & Lomax,
2013; Sullivan et al., 2014); nevertheless, some clergy members were willing to integrate
mental health concepts into their ministries and collaborate with professional counselors
despite their suspicion (Hodge et al., 2020; Kinghorn, 2016). These clergy members
argued that understanding the relationship between religion and psychology was
indispensable for comprehensively meeting the needs of families and individuals living
with mental distress in faith communities (Kinghorn, 2016; Sullivan et al., 2014).
Ultimately, clergy members’ stance on the collaboration between psychology,
counseling, and Christianity comes with potential ramifications for how they interact with
families living with mental distress in their faith communities. Clergy members are
decision-makers regarding what mental resources they are willing to offer to individuals
living with mental distress. They can significantly influence their congregants’ lives, and
their views impact mental health experiences in faith communities.
Mental Health Challenges Across Religions
Researchers who study the relationship between religion and mental distress have
reported consistent findings across the major world religions that indicated patterns in
beliefs that inform how religious people, including clerics, approach mental health
challenges in their religious communities (Koenig et al., 2012). For instance, several

researchers found that religious beliefs determined Christians,’ Jewish, and Muslims’
perceptions of mental distress. Secondly, they found that people’s religious beliefs
informed their help-seeking attitudes. Lastly, they have observed that across Christianity,
Judaism, and Islam, there was a pattern of religion-based explanations for mental distress
for which dependence on God was the cure (see Bayes & Loewenthal, 2013; Kinghorn,
2016; Lim et al., 2018; Rogers-Sirin et al., 2017; Rosmarin et al., 2009; Shebak et al.,
2019).
Jewish people, Christians, and Muslims may have similar experiences in dealing
with mental health challenges because of the similarities in their worldviews
(AbdelKhalek, 2011; Koenig et al., 2012). For example, Rosmarin et al. (2009) found that
for Orthodox Jews and Protestant Christians, religious beliefs and practices accounted for
lower levels of depression they experienced. Also, comparable to Protestants, Orthodox
Jews value a personal relationship with God (Rosmarin et al., 2009). Likewise, Muslims
also relied on their religious beliefs to cope in stressful times (Abu-Raiya & Pargament,
2015). Parveen et al. (2014) found that religiosity in Muslims’ beliefs and practices are
related to fewer mental health problems. Torrecillas et al. (2020) also reported findings
from their study of Hindus, Muslims, and Christian university students that indicated a
connection between Muslims’ and Christians’ reliance on God as a source of support and
the frequency of the experiences of depression.
So, whereas exploring the lived experiences of mental distress within any one of
the world religions is a worthwhile study, I chose to focus on mental distress experiences

within Christianity in this dissertation paper. I explored and described Evangelical
Christians’ experiences of living with another family member’s mental distress. I was
interested in exploring how Evangelical Christians’ religious beliefs and membership in a
faith community influence their self-perception as individuals who live with family
members’ mental health challenges. As I stated in the problem and purpose statement
section, much remains to be explored within Evangelical Christianity about the lived
mental health experiences. Furthermore, I identify as an Evangelical Christian, hence, the
interest in focusing the study on this segment of the U.S. population.
Mental Distress Within Christianity
Traditionally, Christian church leaders have been concerned with worshippers’
welfare and growth in all areas of functioning, including the physical, spiritual, and
psychological domains (Barber & Baker, 2014). Beginning in the Middle Ages, “soul
care” referred to clergy members’ pastoral responsibilities. It applied to all the activities
they performed that resulted in the salvation of a person’s soul (Agılkaya-Sahin, 2016).
As such, “soul care” was the prerogative of church ministers (Lanker, 2019; McRay et
al., 2001).
From a theological perspective, the term soul represents the whole person, the
totality of a person’s being or nature (Lanker, 2019; McRay et al., 2001). Clergy
members served individuals in the faith communities, visiting, guiding, helping address
conflicts, and supporting them to cope with crises and other life transitions; thus, they
approached congregants holistically, caring for them and engaging them through

nurturing and uplifting interactions (Agılkaya-Sahin, 2016; Cole, 2010). “Soul care”
reflected the life and ministry of Jesus, who healed, comforted, guided, and supported
individuals through different life circumstances. Ultimately, the purpose of “soul care”
was to help congregants flourish in their relationship with God, cope with life’s
challenges, live responsibly, and build healthy relationships (Agılkaya-Sahin, 2016).
Mental Distress in Early Christianity
Christians’ perceptions and attitudes toward mental distress have been
inconsistent throughout church history, at times compassionate and, at other times,
persecutory (Covey, 2005; Koenig & Larson, 2001; Putnam, 1885). For example, Putnam
documented that early Christians had varying approaches in their interactions with
individuals in distress. In keeping with biblical teachings, Christians showed compassion
and care for the hungry, the lonely, and the physically sick. Conversely, individuals
experiencing mental distress received no such Christian charity, care, and attention.
Putnam explained this apparent inconsistency of early Christians’ approach to mental
distress by their religious beliefs that promoted demons’ interference in human affairs,
including demon inhabitation of people. To a great extent, the fate of individuals
experiencing mental distress was indistinguishable from those under demonic influence;
consequently, these victimized individuals lived scorned and neglected lives because the
early Christians deemed their suffering to be of demonic influence (Putnam, 1885).
Echoing Putnam’s description of early Christians’ conceptions and attitudes
toward mental distress, Covey (2005) asserted that while the early Christians viewed this

distress as a spiritual illness, a moral failing, or the result of demonic activity at different
times, they have historically taken two stances toward mental distress. They were either
compassionate and accepting of individuals experiencing mental distress or responded to
mental distress experiences punitively (Covey, 2005). For example, in the Middle Ages,
Christians described mental distress as God’s punishment for sin or a battle between good
and evil to control the soul. While Christians were tolerant toward individuals living with
mental distress at first, their attitudes changed to reflect the prevailing popular view that
individuals with mental distress were evil. The change in perspectives caused a change in
their attitudes; as a result, Christians began to discriminate against those experiencing
mental distress. For example, they blamed these individuals for their mental distress,
isolated them, and excluded them from religious assemblies (Covey, 2005). According to
Covey, a literal interpretation of the biblical texts informed Christians’ severe treatment
of those suffering from mental health challenges.
Many other Christians entertained natural causation beliefs about mental distress
already circulating in the Middle Ages. Like their contemporaries, they also believed that
mental distresses were diagnosable conditions with environmental and biological causes
such as humoral imbalance and diagnoses that included melancholy and mania (Kemp,
2019). These medieval Christians did not renounce church teachings about mental
distress and integrated these natural explanations with their religious beliefs (Kemp,
2019). The Renaissance era ushered in new perceptions and attitudes, with Christians
believing that they could treat mental distress through exorcism since it was demonic

(Kemp, 2019). Throughout the Medieval and Renaissance period, Christians and
Christian ethics inspired the establishment of mental hospitals to treat individuals
experiencing mental distress (Covey, 2005).
Mental Distress in the Early U.S. Church
Since the founding years of what is now the United States, clergy members have
been at the forefront of the mental health challenges confronting their congregants
(Covey, 2005; Jimenez, 1986; McGuire & Pace, 2018; Peteet, 2019; Rogers et al., 2012).
Similar to views believers held in Christian communities in the preceding centuries, 18th
century Christians in the United States also explained mental distress primarily by
religious beliefs; hence, it was customary to consider mental distress occurrences as acts
of divine judgment, the devil’s work, a spiritual test, or consequences of personal failings
(Covey, 2005; Jimenez, 1986). As a result, individuals experiencing mental distress were
feared, neglected, and socially isolated (Hartog & Gow, 2005).
Concurrently, the natural and medical explanations for mental distress, which
have taken root in public discourses, rivaled the religious accounts of mental distress.
These explanations included the views that humor-related malfunction caused mental
distress. Influenced by the ideas of their times, as is the case today (Kemp, 2019;
Mathews, 2008; Stanford & Philpott, 2011), many church leaders adapted their views to
accommodate both the supernatural and natural explanations to reflect the common
knowledge about mental distress. Some even encouraged congregants to seek spiritual
care only after medical treatment failed (Jimenez, 1986).

Cotton Mather, a prominent New England Puritan, epitomized this integrated
understanding of mental distress. As a minister, Mather initially held religious causation
beliefs, which included the notion that demonic possession caused mental distress.
Ultimately, Mather incorporated the biological explanations in ascendance during that
period. So, Mather believed in demonic involvement in mental distress experiences and
suggested that malfunctions in the body, such as the vascular and nervous systems or the
hypochondria, could cause mental distress (Jimenez, 1986).
Despite its inconsistent history, Christianity was a beacon of hope for families
experiencing mental distress, and its teaching informed more humane and compassionate
treatment approaches (Koenig & Larson, 2001). For example, moral treatment was the
first form of psychiatric care for individuals experiencing mental distress in the United
States in the 18th and 19th centuries. It was a treatment approach built upon Protestant
ethics and Christian virtues such as kindness and dignity (Koenig & Larson, 2001;
Tanaquil, 1998). Also, Christian leaders were influential in establishing mental hospitals,
with Christians serving as administrators who implemented religious interventions that
included church attendance and listening to Bible sermons (Koenig & Larson, 2001;
Tanaquil, 1998).
Nonetheless, with the increased influence of natural explanations of mental
distress, nurses and doctors became the primary care providers in place of church leaders
and family members (Covey, 2005). This change marked a turning point in the role of
church leaders in addressing mental distress in their communities. Even though religious

beliefs were no longer the only way to explain mental distress, spiritual and moral
interpretations persisted. The treatment options available to Christians experiencing
mental distress and their families were primarily religious, involving prayer, fasting, and
social support from church leaders (Covey, 2005; Jimenez, 1986).
Mental Distress in Present-Day U.S. Evangelicalism: A Continuum of Beliefs
Strategies in U.S. churches to tackle the mental health challenges depend largely
on church leaders’ interpretation of biblical teachings and their stance on psychology
(Kinghorn, 2016). In 2015, 25% of U.S. adults (n = 61 million) claimed association with
Evangelical denominations, representing 55% (n =113 million) of all Protestants (Pew
Research Center, 2015). Whether they are clergy members or congregants, an appraisal
of Evangelical Christians’ perceptions of mental distress suggests there is in the church a
range of causation beliefs such as demonic activity, spiritual warfare, sinful living,
biological and psychological factors (Avent et al., 2015; Stanford & Philpott, 2011; Trice
& Bjorck, 2006; Wesselmann & Graziano, 2010). Thus, the causation beliefs about
mental distress and church engagement with those experiencing mental distress will be as
diverse as the denominational traditions and theological beliefs within U.S.
Evangelicalism.
Perceptions of Mental Distress. There is a consensus in the literature about the
relationship between a person’s religious beliefs and their perception of mental distress.
Many researchers have suggested that people’s religious affiliation informs their opinions
about mental distress (Mathews, 2008; Stanford & Philpott, 2011; Wesselmann &

Graziano, 2010). For instance, Pentecostals, a group of Protestant Christians who
subscribe to Evangelicalism, conceptualize mental distress as a function of the
environment in which people live, far more often than attributing it to spiritual and
biological causes. Trice and Bjorck (2006) examined Pentecostal Christians’ perspectives
on the causes and treatments for depression. They remarked that participants who
adhered to Pentecostal theologies attributed the primary causes of depression to social
and psychological factors such as rape and physical and sexual abuse. Spiritual
explanations (i.e., demonic possession or acts of God) ranked lower on participants’ list
of causation beliefs.
Compared to Pentecostals, Evangelical Christians were far more likely to attribute
spiritual causes to mental distress. In one of the earliest studies of its kind to examine
Christians' experiences with mental distress in faith communities, Stanford and McAlister
(2008) found that 70.5% (n = 60) of participants said fellow congregants suggested that
mental distress resulted from personal sin or demonic activity. In another study,
Wesselmann and Graziano (2010) also found that Evangelical Christians attributed
mental distress to sinful or immoral behaviors.
Additionally, Wesselmann and Graziano (2010) found that participants who held
religious causation beliefs about one type of mental distress did so about the others. For
these Evangelical Christians, mental distress results from sin or moral failings, regardless
of its type. Wesselmann et al. (2015) published the findings of their investigation of
peoples’ beliefs about mental distress and the social support they were willing to give to

individuals experiencing mental distress. Compared to mainstream Protestant Christians,
Evangelical participants were more likely to endorse religious explanations of mental
distress and offer religious-based support. These results provided further evidence of the
connection between people’s religious beliefs and their perception of mental distress.
Clergy members’ and faith leaders’ perspectives about mental distress mirror the
diversity of beliefs observable in parishioners. For example, in 2005, Hartog and Gow
explored the relationship between religion and mental health, focusing on the connection
between religious beliefs, religious values, and beliefs about the causes and treatments of
mental distress. After evaluating 126 Protestant Christians’ beliefs about causal and
treatment preferences for major depression and schizophrenia, they concluded that clergy
members’ religious beliefs and values were the lenses through which they conceptualized
mental distress, its causes, and treatment interventions.
Similarly, Mathews (2008) examined 213 Singaporeans and theologically
conservative pastors’ views of mental distress and found that the pastors relied on their
religious beliefs to explain mental distress. Most pastors attributed mental distress to
godless living, personal responsibility, and failures to learn from past events. A small
minority among the pastors believed in demonic activity in mental distress.
Stanford and Philpott (2011) surveyed senior pastors of a Baptist denomination in
Texas. They reported that these pastors deemed biological factors more contributory to
mental distress than psychosocial and spiritual causes. Conversely, Avent et al. (2015)
found that African American Protestant pastors believed mental distress resulted

primarily from spiritual and religious determinants, such as lack of faith, demonic
activity, and spiritual warfare.
Pastors’ race and denominational affiliation also influence clergy causation beliefs
about mental distress. Payne (2009) examined 204 Protestant pastors’ understanding of
the causes of depression, focusing on participants’ race and religious affiliation. They
suggested that race and denomination influenced the pastors’ views on the etiology of
depression, with their religious affiliation being the most determining factor. Payne and
Hays (2016) analyzed the conversations of 35 U.S. pastors on an online social media
platform. They discovered that the pastors described a broad scope of beliefs about the
causes of mental distress ranging from religious (i.e., demonic activity, moral failings,
and sin) to biomedical and socio-relational factors (i.e., traumatic life events).
The researchers of the studies above highlight the diversity of views about mental
distress within Evangelicalism. Religious accounts of mental distress, specifically,
demonic possession causation beliefs, were once the predominant view among early
Christians; however, much of the recent literature on Evangelicals and mental distress
signals a shift toward a less spiritualization of mental distress experiences. Many
Christian denominations, including Evangelicals, began distancing themselves from an
over spiritualization of mental distress (Mathews, 2008; Stanford & Philpott, 2011). Most
recently, Lloyd and Waller (2020) observed an increasingly diverse view of the causes of
mental distress among British Evangelical Christians, similar to studies conducted in the

United States (Santos & Kalibatseva, 2019; Stanford & Philpott, 2011; Trice & Bjorck,
2006).
Together, these studies offer pertinent information about the variation in pastors’
conceptualization of mental distress. The more conservative the religious beliefs and
denominational practices to which people adhere, the more religious their causation
beliefs about mental distress. Views about mental distress and attributions regarding the
causes and treatments for mental distress are on a continuum (Hartog & Gow, 2005;
Stanford & McAlister, 2008; Wesselmann et al., 2015).
Attitudes and Engagement with Mental Distress. Attitude refers to
disposition, a manner in which an individual performs or approaches a person,
situation, or object (Musgrove, 1998). A noteworthy conclusion from the literature
review on mental distress and Christianity is that Christians’ religious beliefs shape
their understanding of mental distress (Adams et al., 2018; Payne & Hays, 2016;
Wesselmann & Graziano, 2010). Furthermore, those beliefs significantly impact how
Christians view mental health challenges, including their responses to mental
distress in their faith communities (Hays & Payne, 2020; Payne, 2009; Wesselmann
et al., 2015).
Clergy Members’ Attitudes and Engagement With Mental Distress. As first
responders to congregants’ mental health challenges, understanding clergy members’
attitude about mental distress is essential to the conversations about mental health in their
faith communities (Hodge et al., 2020; Royal & Thompson, 2012; Sullivan et al., 2014;
Wang et al., 2003). Indeed, Evangelical pastors’ attitudes can vary vastly from: (a) a

pastor’s desire to increase their knowledge (McRay et al., 2001; Stanford & Philpott,
2011), (b) indifference (Rogers et al., 2012), and (c) to the pastor’s dismissal of people’s
mental distress experiences (Jones et al., 2012; Rogers et al., 2012; Stanford &
McAlister, 2008). Such attitudes will likely affect the experiences of families living with
mental distress, their participation in church life, and the support they receive from fellow
congregants.
Mental Health Programming and Support Resources. Few churches in the
United States have structures to adequately respond to the needs of people experiencing
mental distress (Frenk, 2014). Only 1 in 4 U.S. religious congregations, comprising Black
Protestant, Roman Catholic, mainstream Protestant, and conservative Protestant churches,
offer supportive services for congregants’ mental health needs (Wong et al., 2018).
Within U.S. Evangelicalism, clergy members often take two primary approaches to
confront mental distress in their congregations (Kinghorn, 2016). On the one hand, clergy
members may adopt an integrationist approach in their ministry to congregants. Such an
approach to pastoral care involves applying psychiatric and psychological concepts and
interventions compatible with Christian beliefs (Kinghorn, 2016; McMinn et al., 2010).
For example, a pastor who attributes mental distress to both biopsychosocial and spiritual
causes is more likely to endorse treatment interventions that include practicing spiritual
coping methods, professional mental health counseling, and psychotropic medication
(Sullivan et al., 2014).

On the other hand, clergy members who endorse spiritual explanations for mental
distress are more likely to advocate for religiously based treatment approaches. They are
conservative in their beliefs, often displaying an antipsychology and antipsychiatry
stance. Furthermore, these pastors may also hold stigmatizing views, which indicates
their lack of adequate knowledge about mental distress (Freeman & Baldwin, 2020; Jones
et al., 2012; Stanford & Philpott, 2011). They may also embrace a biblical counseling
approach in their church ministries for pastoral care. Biblical counseling began as a
movement within Evangelical churches with the work of Jay Adams in the 1960s and
1970s. Adams took the position that sin was the root cause of all human problems and
contended that closeness with God was the ultimate solution (Greggo & Sisemore, 2012;
Weaver, 2011). Therefore, biblical counseling proponents may reject any association with
secular psychology or psychiatry and affirm the congregant’s personal responsibility to
address life’s problems. They view the Bible as sufficient and the ultimate resource for
pastors in dealing with congregants’ issues, including mental health conditions (Greggo
& Sisemore, 2012; Kinghorn, 2016; Weaver, 2011).
Personal Factors Influencing Clergy Members’ Engagement. Hays and Payne
(2020) examined clergy members’ characteristics and identified specific qualities that
distinguish them in their engagement with individuals experiencing mental distress. They
found that humble and transparent clergy members, clergy members with personal
experiences dealing with challenging situations, and clergy members willing to increase
their understanding of mental health challenges respond more appropriately to

congregants’ mental health needs. Additionally, emotionally intelligent clergy members
are more likely to prioritize mental health and approach congregants’ mental health
challenges with a greater sense of urgency (Hays & Payne, 2020).
Jones et al. (2012) found a connection between clergy members’ ability to
recognize mental distress and the interventions they use. Their finding supports Jorm’s
(2000) assertion that low mental health literacy may be a barrier to providing adequate
mental health care to those in need. As Vermaas et al. (2017) proposed, clergy members
would benefit from mental health literacy training to competently attend to their
congregants’ mental health needs. Accurate knowledge of mental distress causes is
essential for clergy members to affirm and support congregants’ experiences with mental
distress (Payne, 2009; Stanford & Philpott, 2011; Taylor & Stanton, 2007).
In all, clergy members’ engagement with congregants’ mental health needs
reflects their interpretation of the biblical text and beliefs about psychiatry and
psychology’s role in addressing human problems (Sullivan et al., 2014). The quality and
level of their engagement depend on their mental distress causation beliefs. As such,
clergy members can promote or hinder congregants’ access to mental health services
(Payne, 2009). The more conservative the religious leaders, the fiercer the opposition to
integrating psychology to enhance their pastoral ministries (Hodge et al., 2020);
nevertheless, clergy members better equipped to help their congregants benefit from a
wide range of available supportive services often embrace psychology and professional
mental health (Payne & Hays, 2016).

Congregants’ Attitudes and Engagement With Mental Distress. Several scholars
have examined the benefits and challenges of church membership (Freeze, 2017;
Hayward & Krause, 2015; Krause, 2009; Merino, 2014). A faith community is a source
of support for individuals in times of need (Krause, 2009; Merino, 2014). Membership to
a faith community contributes to the sense of connection and emotional well-being a
person enjoys from identifying with a larger group of individuals (Obst & Tham, 2009).
In this large group, members cultivate interpersonal relationships and receive acceptance,
support, and care from one another (Gailliard & Davis, 2017). Belonging to a faith
community increases members’ chances of building social bonds connections with
individuals with shared values and beliefs; consequently, the deeper a person’s
relationships with other faith community members, the greater their well-being (Obst &
Tham, 2009).
Although the literature bears evidence of the benefits of belonging and
participating in faith communities, it is worth stating that faith communities are not
necessarily friendly places for everyone. As Webb et al. (2011) remarked, a faith
community can be a social connectivity source for some but a lonely place for others.
Krause et al. (1998), Krause and Hayward (2012a), and Krause (2014) have also
documented the effects of negative interactions on congregants’ mental health in faith
communities. Like clergy members, congregants’ attitudes toward individuals living with
mental health conditions and their families reflect their causation beliefs. Adams et al.
(2018) studied students in a Christian college setting. They exposed the students’

stigmatizing attitudes toward people living with schizophrenia, explaining that the more
conservative the beliefs, the more stigmatizing the attitudes toward mental distress.
Accounts of mental distress within Evangelicalism are not monolithic across all
Evangelical churches. Church leaders have diverse positions on mental distress based on
the congregation’s characteristics, such as religious traditions and theological beliefs, for
instance (Lefevor et al., 2020; Santos & Kalibatseva, 2019; Stanford & Philpott, 2011).
The teachings about mental distress in their faith community, the quality of interactions
within their faith communities, and fellow parishioners’ attitudes toward mental distress
inevitably influence how family members live with mental distress and make sense of
their experiences (Lloyd & Waller, 2020; Rogers et al., 2012; Stetz et al., 2011).
Mental Distress Stigma
There is corroborating evidence in the literature suggesting that families and
individuals experiencing mental distress have had unpleasant experiences in faith
communities. For example, there were instances of rejection and abandonment (Rogers et
al., 2012), a devaluation or denial of peoples’ mental distress experiences (Stanford &
McAlister, 2008), a withholding of social support (Wesselmann et al., 2015), and mental
distress stigma (Freeman & Baldwin, 2020; Stanford, 2007; Wesselmann & Graziano,
2010). Goffman (1963) defined stigma as “an attribute that is deeply discrediting,” an
undesirable attribute that interferes adversely with a person’s social life and their
interactions with others (p. 3). Stigma marks individuals as different and implies a

debasement of their identity. The effect is social disapproval at the individual,
interpersonal, and societal levels (Bos et al., 2013; Goffman, 1963).
Researchers who have studied the stigma of mental distress characterized it as a
social construct involving stereotyping beliefs, prejudicial emotional reactions, and
discriminatory treatment toward stigmatized individuals (Fox et al., 2018). Accordingly,
individuals experiencing mental distress are deemed unfit, weak, and dangerous and
likely to be subject to pity, dread, and hostility from people in their communities.
Moreover, they often lack support and experience social exclusion (Fox et al., 2018).
Finally, mental distress stigma is harmful to these individuals’ self-esteem and
selfefficacy. It can also exacerbate their mental distress symptoms (Marcussen et al.,
2018). The literature on stigma research also suggests that parents, spouses, and children
experience stigma by association with the family member with mental distress (Bos et al.,
2013; Sanden et al., 2015).
Christians’ perceptions of mental distress are connected to the biblical teachings
that shaped their religious beliefs (Cohen, n.d.; Payne & Hays, 2016). In turn, these
religious beliefs mediate how people make sense of mental distress and adopt an attitude
towards people experiencing mental distress (Hartog & Gow, 2005; Wesselmann et al.,
2015). Within U.S. Evangelicalism, individuals who hold conservative religious beliefs
or explain mental distress solely through their religious beliefs are more likely to
stigmatize people living with a family member experiencing mental distress (Adams et
al., 2018; Freeman & Baldwin, 2020; Stanford, 2007; Wesselmann & Graziano, 2010).

However, stigmatization of mental distress is not a new occurrence within
Evangelicalism (Covey, 2005; Koenig & Larson, 2001; Putnam, 1885). Today, many
parishioners and church leaders in faith communities continue to endorse stigmatizing
views of mental distress; as a result, individuals living with mental distress and their
families experience additional stress (Freeman & Baldwin, 2020; McGuire & Pace, 2018;
Rogers et al., 2012).
In sum, it is arguably impossible to overstate the centrality of the interpretations
of the biblical texts in Evangelical Christians’ conceptualization of mental distress. These
texts informed many Evangelical Christians’ attitudes and perceptions of mental distress.
Whether they are clergy members or congregants, religious beliefs and attitudes affect
how people engage with individuals experiencing mental distress and their family
members. When the church fails to attend to the needs of families and individuals living
with mental distress, starting with acknowledging their experiences, they are disheartened
and distance themselves from their faith communities (Rogers et al., 2012; Stanford &
McAlister, 2008). Many believers in Evangelical faith communities, including clergy
members, appear to have inadequate mental health literacy viewing mental distress as a
temporary condition that disappears eventually (Jones et al., 2012; Royal & Thompson,
2012).
Given such views and attitudes about mental distress, it might be fair to assume
that mental distress stigma would be rampant in faith communities. That being the case,
conducting a qualitative study to explore the lived experiences of individuals living with

a family member experiencing mental distress in faith communities is perhaps more than
an academic exercise. In some small ways, this study I proposed can provide an
opportunity for prospective participants to become a voice for others, who, for various
reasons specific to their circumstances, are afraid to make their stories public in their faith
communities. Christians in faith communities have much to learn about mental distress
from those experiencing it. In that respect, I believe that until people in faith communities
see mental distress through the perspectives of those living with it, their attitudes may
continue to be stigmatizing, depriving fellow congregants of much-needed support
(Rogers et al., 2012; Wesselmann et al., 2015).
Mental Distress in the Family
The effects of mental distress on families are multidimensional, namely,
economic, social, and psychological. For example, Fekadu et al. (2019) found that family
members of individuals experiencing mental distress suffered job instability, financial
difficulties, deterioration of physical health, and increased psychological problems such
as depression. They also encountered dysfunctions in family and social relationships,
including marital problems and poor family cohesion (Fekadu et al., 2019). Such findings
support Kerr and Bowen’s (1988) description of the family as an emotional unit of
individuals with functional positions and responsibilities that influence their biological,
psychological, and social functioning. As such, distress in a person’s life obstructs other
individuals’ functioning in the family (Crowe & Lyness, 2014; Fekadu et al., 2019).

Mental distress in a family can fracture that family’s identity. Family members
may be friendly but distant and close but avoidant toward each other (Sporer & Toller,
2017). Undiagnosed family members may be ambivalent about their caregiving
responsibilities vis-à-vis the family member experiencing mental distress (Sporer &
Toller, 2017; Stein et al., 2020). The disruption in family identity and members’
functioning is acute if they live in the same home with the person experiencing mental
distress (Corrigan & Miller, 2004; Sanden et al., 2015).
Family Functioning
Family functioning refers to the reciprocal process of interactions between family
members that sustains successful daily living (Kivelä et al., 2018). According to
Pakenham and Cox (2014), family functioning in a household where a member is
experiencing mental distress tends to be more dysfunctional than in a home without
mental distress. Several researchers have documented the difficulties confronting such a
family. For instance, Cohen et al. (2011) and Liegghio (2017) reported that these families
experienced a gamut of challenges and needs, including lack of social support, inadequate
communication, emotional distance, and significant disruption of life activities. In these
families, members reported despair and dissatisfaction with their lives. Crowe and Lyness
(2014) and Saunders (2003) wrote that these family members faced psychological
distress, deteriorating well-being, isolation, and disruption in family functioning, while
Liegghio (2017) and Saunders and Byrne (2002) showed that family members of people
living with mental distress experienced anger, fear, anxiety, and uncertainty. Despite

these challenges, Power et al. (2016) and Saunders and Byrne found that social support,
whether from friends, neighbors, or mental health professionals, contributed to family
members’ positive experiences living with another member’s mental distress.
Stigma in the Family
Family members of people living with mental distress may often experience
significant shame and avoidance. Whether they are the parents, siblings, or children
living with another person’s mental distress, they may be subject to stereotyping beliefs
that shame or blame them for the family member’s mental distress experiences (Corrigan
& Miller, 2004; Muralidharan et al., 2016). Stigma-related experiences and beliefs caused
the most distress for family members. Generally, the more intense the stigmatization
experience, the less empowered family members feel, and the less support and cohesion
family members may share (Muralidharan et al., 2016).
In agreement with Muralidharan et al. (2016), Sanden et al. (2015) observed that
family members of people living with mental distress routinely experienced stressful and
unpleasant social interactions with a negative impact on their well-being; consequently,
they avoided social relationships, preferring to live in isolation rather than undergo public
humiliation (Sanden et al., 2015). Furthermore, they often chose a life of secrecy,
preferring to hide their relationship with the individual with the mental distress’
experiences (Corrigan & Miller, 2004; Lukens et al., 2004).
In addition to the mental distress stigma from friends, neighbors, and individuals
in faith communities (Corrigan & Miller, 2004; Lukens et al., 2004), Sanden et al. (2015)

found that these families experienced stigma attitudes from mental health professionals.
Like Sanden et al., Liegghio (2017) observed that many mental health professionals have
often neglected family members’ mental health needs or concerns. Indeed, mental health
professionals can exhibit stigmatizing attitudes such as blaming or shaming individuals
living with mental distress and their families, showing a lack of interest and respect, or
being annoyed with their request for services or information (Charles, 2013; Kopera et
al., 2015). Whether overt or covert, mental health professionals’ stigmatizing attitudes
toward mental distress can hinder treatment-seeking (Clement et al., 2015; Corrigan et
al., 2014; Wang et al., 2018).
Coping and Adjustment in Family Functioning
Coping refers to thoughts and behaviors or actions individuals take in response to
stressful situations and demands. People can use coping effectively to facilitate and
regulate their emotional reactions to perceived stress (Folkman et al., 1986; Folkman &
Moskowitz, 2004; Taylor & Stanton, 2007); however, maladaptive coping such as denial
and avoidance can worsen the life satisfaction of individuals living with a family member
experiencing mental distress. Inversely positive reframing, acceptance, and seeking
emotional support can help reduce related stressors, resulting in improved life satisfaction
(van der Sanden et al., 2013). Crowe and Lyness (2014) explored the coping strategies
associated with better functioning in families living with mental distress. They observed
that family support increased in families in which members maintained close

relationships with each other. In such families, family cohesion fostered members’ ability
to positively reframe mental distress, ultimately resulting in greater family satisfaction
(Crowe & Lyness, 2014).
Findings from Sanden et al.’s (2015) study showed that individuals living with a
family member who experienced mental distress also faced stigma. For example,
outsiders labeled family members of a person experiencing mental distress as eccentric.
Moreover, parents, mostly mothers, bore the blame for their family member’s mental
health conditions (Sanden et al., 2015). Van der Sanden et al. (2013) examined how
family members coped with the effects of stigma by association. They found that family
members of people experiencing mental distress faced depression, anxiety, and loss of
behavioral and emotional control because of stigma by their association. Such exposure
to stigma negatively affected their functioning, including their view of self, expectations,
and life goals. As the family members attempted to cope and adjust to mental distress,
they would often take actions to normalize their living situation and improve their
functioning, such as seeking social support (van der Sanden et al., 2013).
According to Saunders (2003) and Raymond et al. (2017), families living with
mental distress would continuously adjust and adapt to their mental health challenges or
needs. Although such adjustment would be taxing, Saunders believed efforts to
accommodate the family’s changing needs would improve functioning, even increasing
family resiliency. Jonker and Greeff (2009) studied the adaptation process in families
living with mental distress and identified internal resources and external resources that

facilitated their resilience. For example, relying on spirituality and religious belief
supported family members’ efforts to care for the member experiencing mental distress
and accommodate mental health needs. Also, family members’ attitude and commitment
to hope and persevere through the difficulties fostered family resilience. Lastly, the
ability of families living with the mental distress of another member to cooperate and
express mutual support, love, and respect enabled family adaptation. Regarding the
external resources, social support and mental health services in their community proved
instrumental in helping family members adjust to the disruptions in family functioning.
In contrast to Jonker and Greeff (2009), who studied the adjustment process in the
family unit, Stein et al. (2020) focused on individual adjustment in siblings of adults
living with mental distress. The results from Stein et al.’s study suggested that siblings’
adjustment depended on the quality of their relationship with their sister or brother living
with mental distress, their belief about the severity of the mental health problems, and the
intensity of their ambivalence toward playing a caregiving role. Stein et al. stated that
siblings without mental health conditions showed less affection, engaged in more
frequent conflict, and reported more significant personal loss when they believed their
sibling had better control of the mental distress symptoms.
Other scholars contributed further to our understanding of the process of family
adaptation. For example, Power et al. (2016) found that family members’ open
communication about their experience of mental distress, their ability to manage family
relationships, access social support, and address their feelings of shame facilitated family

resilience. In another study involving families of children diagnosed with an autism
spectrum disorder, Whitehead et al. (2015) found that members who proactively
implemented solutions to meet their familial obligations and addressed mental health
needs experienced resilience.
Parents’ Experiences of Children’s Mental Distress. The adverse impact of
children’s mental distress affects many areas of a parent’s daily life, including personal,
financial, and social (Richardson et al., 2013). These parents struggled with issues of
identity, loss of self, confidence, and loss of control. For example, parents reported anger
and guilt regarding their children’s mental health conditions, which were exacerbated by
the accompanying persistent grief over the loss of their child’s selfhood, personality, and
deferred dreams (Richardson et al., 2013). Also, Eaton et al. (2016) found that mothers of
children with emotional and behavioral disorders viewed themselves as failed parents.
They were doubtful of their ability to parent their children.
As Moses (2011) stated, parents’ attitudes towards their children’s mental distress,
their response to the challenges they confronted, and the treatment they sought reflected
their causation beliefs about their children’s mental health. Whether they viewed their
children’s mental distress as a temporary or permanent condition, rejected or embraced
medical explanations to make sense of their experiences, all parents faced a range of
feelings, including worry, sadness, guilt, and shame (Moses, 2011). Financially, the cost
of treatment was a burden that disrupted parents’ well-being and functioning (Richardson
et al., 2013). Socially, the parents described a lack of social support due to stigma, which

they also experienced from mental health professionals (Richardson et al., 2013). These
parents also experienced self-stigma with adverse consequences for their self-esteem,
self-efficacy, and well-being (Eaton et al., 2016).
Furthermore, people discounted these parents’ needs as all efforts and attention
went toward attending to the children’s mental distress (Richardson et al., 2013).
According to Rodríguez-Meirinhos et al.’s (2018) findings, these needs included lacking
information about their children's mental distress and its impact on the family, social and
emotional support, and mental health professionals to listen to their views regarding
treatment planning. In all, these challenges further reduced the parents’ limited resources
to attend to the needs of their child’s mental distress experiences (Richardson et al.,
2013).
Siblings’ Experiences of Mental Distress. Sibling relationships affect the family
system and the well-being of all its members (Feinberg et al., 2012). According to Buist
et al. (2013), sibling relationships are essential to understanding how families function
and adjust to the destabilizing impact of mental distress. For example, Gass et al. (2007)
and Bojanowski et al. (2020) found sibling relationships to be a source of emotional
support and stability because the affectional bond between siblings plays a moderating
and protective role in children’s responses to stressful events. However, siblings living
with a brother or sister’s mental distress face significant risks and challenges because the
relationship among siblings influences their overall social functioning. One sibling’s
behavior affects the mental health of the other (Feinberg et al., 2012). Friedrich et al.

(2008), Ma et al. (2015), and Ma et al. (2020) observed that these siblings experienced a
decline in functioning and were at a higher risk of developing mental health problems
because of a brother or sister’s mental distress. In fact, according to Ma et al. (2016), 1 in
3 siblings of individuals experiencing mental distress also had mental health problems of
their own.
The effects of living with a brother or sister’s mental distress are pervasive,
disrupting critical aspects of the other sibling’s functioning. For example, siblings living
with a brother or sister’s mental distress experienced loss, chaos, and helplessness
(Lukens et al., 2004) and struggled with stress, shame, and worry, as they bore the stigma
and burden of their sibling’s mental distress (Liegghio, 2017; Sanden et al., 2015). They
also had difficulty making sense of their sibling’s distress, which they described as bad
(Liegghio, 2017). Lastly, they were ambivalent and conflicted, experiencing guilt and
anger about their life circumstances (Lukens et al., 2004; Ma et al., 2015). The siblings
expressed negative views of their brother or sister’s mental health experiences and
viewed their family as flawed (Liegghio, 2017). They reported a sense of abandonment as
their parents devoted much of the family resources to their brother or sister’s care
(Lukens et al., 2004; Ma et al., 2015). Lastly, they expressed complex communication
issues as they struggled to talk openly about their sister or brother’s mental health
challenges (Liegghio, 2017; Ma et al., 2015).
Socially, the siblings of an individual with mental distress tend to avoid social
interactions because of mental distress stigma (Sanden et al., 2015). The stigma they

experienced from friends contributed to the sadness and disappointment that affected
their social relationships (Lukens et al., 2004). While they worried about an uncertain
future as they continued to live with the burden of mental distress (Lukens et al., 2004;
Ma et al., 2015), their concerns and needs often went unnoticed even by professionals in
the mental health community (Cox, 2010).
Despite the debilitating and life-altering challenges of living with a brother or
sister’s mental distress, siblings reported some potential benefits to their lives. For
example, Lukens et al. (2004) reported that some siblings found meaning in their
experiences. Other siblings noticed a greater family cohesion as members made concerted
efforts to help the family function better (Lukens et al., 2004).
Children’s Experiences of Mental Distress. In the United States, approximately
5 million children live with parental mental distress (Sherman & Hooker, 2018). The
literature reported that children of parents with mental distress were more likely to
develop mental health problems (Amrock & Weitzman, 2014; Johnson et al., 2018;
Santvoort et al., 2015). First, Amrock and Weitzman (2014) showed that the mental
distress of either a father or mother increased the probability of mental health issues in
their children. Likewise, Johnson et al. (2018) examined Australian children aged 4 to 17
and found a higher occurrence of mental health issues in children whose parents had
mental distress diagnoses. Secondly, Rasic et al. (2014) noted that 1 in 2 children living
with parental mental distress was at risk of developing mental health problems by early

adulthood. Lastly, Maybery et al. (2009) suggested that these children were twice as
likely to have mental health problems than those in households without mental distress.
Children attributed the causes of their parents’ mental distress to social and
environmental factors (Gladstone et al., 2011); nevertheless, their knowledge of mental
distress remained limited as their parents and adults in their lives preferred to withhold
pertinent information from them. They recognized mental distress by noticing the
volatility in their parents’ behaviors (Mordoch, 2010; Power et al., 2016). Their mental
distress experiences depended on several factors, including their age, available social
support, type of parental mental distress, and developmental abilities (Rasic et al., 2014;
Yamamoto & Keogh, 2018). Yamamoto and Keogh (2018) indicated that children living
with parental mental distress experienced a range of emotions from worry and
bewilderment to love and hope. Mordoch (2010) explained that for the children, mental
distress in the home indicated unpredictability, declining parental functioning, and
fluctuations in physical health.
Children bore additional responsibilities and the emotional burden of caring for a
younger sibling or doing more household tasks due to parental mental distress (Afzelius
et al., 2018; Mordoch & Hall, 2008; Yamamoto & Keogh, 2018). Also, these children felt
responsible for the worsening of their parents’ mental health conditions, so they made
efforts not to appear as a burden and tried to be strong for their parents’ sake, often
concealing their frustrations and concerns (Yamamoto & Keogh, 2018). Additionally,

they lived with mental distress stigma from relatives and friends (Mordoch & Hall, 2008;
Yamamoto & Keogh, 2018).
To manage the stress of living with parental mental distress, the children coped
with positive activities such as playing sports or sharing their concerns with a trustworthy
person (Yamamoto & Keogh, 2018). Most of these children demonstrated flexibility and
resilience. They strived to adjust to the parents’ mental health conditions and abrupt shifts
in family functioning (Afzelius et al., 2018; Gladstone et al., 2011). They were
continually adjusting to fluctuations of their parents’ mental distress experiences and
creating a safe and stable world for themselves where they could explore their identity
(Afzelius et al., 2018; Mordoch & Hall, 2008). They valued the relationship with their
parents and any love and support they received from them; however, they managed to
protect their unique identity despite living in a destabilizing environment. They took
active steps to maintain their emotional well-being by monitoring their parents’
symptoms and behaviors and making the necessary adjustments (Mordoch & Hall, 2008).
They also coped by withdrawing into their safe spaces and engaging in activities such as
drawing or listening to music (Afzelius et al., 2018) and pursuing their own interests, and
rejecting responsibilities beyond their age (Mordoch & Hall, 2008). Despite the
instability in the home and an uncertain future, the children reframed their experience as
an opportunity for growth (Yamamoto & Keogh, 2018).
Nevertheless, not all children living with parental mental distress resorted to
positive coping practices. For instance, some resorted to maladaptive coping strategies

such as substance use to medicate their pain (Yamamoto & Keogh, 2018). Many others
withdrew from social interactions because of mental distress stigma (Yamamoto &
Keogh, 2018). Children living with parental distress often lack social support and receive
little support from mental health professionals (Yamamoto & Keogh, 2018).
In sum, the literature review on mental distress in the family showed some
consistent findings. First, mental distress in the home affects everyone with varying
degrees of effects on family members. Second, mental distress affects all levels of the
family structure and disrupts its normal functioning. Third, some secrecy surrounds a
family member’s mental distress due to fear of judgment, stigma, and lack of
understanding. Last, all the family members of individuals living with mental distress
lack social support. They also feel a lack of support from mental health professionals,
who, in some cases, exhibit stigmatizing views and attitudes toward family members.
My study’s setting was primarily in the family context because, as the extant
literature on family experiences of mental distress showed, mental distress affects all
family members. Findings can inform how mental health professionals and clergy
members support or address the needs of family members of individuals experiencing
mental distress. Furthermore, because a family is an emotional system, improved
functioning in non-diagnosed family members can positively affect family members,
including the individual experiencing mental distress (Kerr & Bowen, 1988; Waters,
2020). As such, understanding mental distress from non-diagnosed family members’
perspectives may have many benefits.

Experience of Christian Families Living With Mental Distress
Rogers et al. (2012) piloted a quantitative study using data collected between
2008-2010 to investigate the experiences and functioning of Christian families caring for
the family member living with mental distress in the context of their faith communities.
Altogether, 5899 adult family members representing 24 Protestant churches from 10 U.S.
states participated in this study. They were church members of Baptist, Lutheran, and
nondenominational congregations.
The study participants completed the Church Census, a self-report tool that identified the
demographic characteristics of congregation families, their needs, strengths, and
expectations from fellow congregants. Additionally, Rogers et al. (2012) used two self-
report measures. First, they administered the Family Strengths Scale to measure family
functioning categories such as family cohesion, conflictual communication, adaptability
and flexibility, and community connections. Secondly, participants took the Christian
Faith Practices that assessed faith behaviors, which included family spiritual practices.
Rogers et al. divided participants into two groups. The first group, labeled the depression
and emotional problems group, were comprised of family members who reported
difficulties in the family due to mental distress. The second group was the control group.
They were the rest of the participants who were without family mental distress.
Rogers et al. (2012) found that about 27% (n = 1,593) of 5,889 respondents
reported having family members coping with depression or other serious emotional
problems. These participants experienced more emotional problems, financial difficulties,

and frequent relationship conflicts than respondents in the control group. Respondents
with mental distress in the family reported a negative impact on their spiritual practices
and church involvement. This research presented a startling picture of mental distress in
the faith communities. Families coping with a member’s mental distress were invisible in
their faith communities as clergy members and fellow congregants discounted their
mental health needs. They provided little emotional support to families with mental
distress; consequently, family members were isolated further and participated less in
church activities.
Rogers et al. (2012) gave a voice to families to share their experiences of mental
distress. As Rogers et al. indicated, such personal stories are a source of meaning and
hope for struggling individuals. Also, Rogers et al.’s findings highlighted social support
as an essential contributing element to the better functioning of families living with a
family member experiencing mental distress in faith communities. Such support from
fellow congregants, whether in the form of friendships or being there (presence) for
families with mental distress, may help reduce isolation and stigma.
Using a survey research design, Rogers et al. (2012) successfully gathered
information from a sample of Evangelical Christians to describe the characteristics of
families living with mental distress of a member in faith communities. They found that
families living with mental distress face many needs and challenges in faith communities.
The results exposed clergy members’ and congregants’ failure to attend to the needs of
these families adequately. Finally, Rogers et al. suggested potential collaboration

opportunities between faith and mental health communities. They provided a framework
for developing such collaboration, which Roger et al. said, must begin with mental health
professionals and clergy members building constructive relationships.
Notably, Rogers et al. (2012) did not examine the coping strategies of families
living with a member’s mental distress. They did not address the mental health needs or
other difficulties family members experienced at home and their impact on their faith
community involvement. Lastly, a significant limitation of the study is related to the
research design, which did not allow the researchers to explore the particularities in each
participant's unique experiences.
Lloyd and Waller (2020) conducted a quantitative survey study to examine church
teachings that endorsed spiritual explanations of mental distress and their effect on
congregants’ relationships within faith communities and their beliefs about engagement
with professional mental health practitioners. They surveyed 446 British Evangelical
Christians, 72% (n = 321) of whom were female, 27% (n = 120) male, and 1% (n = 5)
other. Participants attended church services regularly and represented different
evangelical faith communities that included Anglican, Baptist, Pentecostal, and
nondenominational Christians. About 9% (n = 40) of the respondents indicated that they
participated in the anonymous online survey because of a family member’s mental
distress.
Lloyd and Waller (2020) found that over 56% (n = 250) of participants indicated
that the views and attitudes about mental distress in their faith community were pleasant,

while 64% (n = 285) believed their church communities supported them in seeking
professional help. However, about 34% (n = 152) of participants indicated church
teachings presented mental distress as a spiritual problem, and 31% (n = 138) offered
spiritual solutions such as prayer and exorcism.
Lloyd and Waller’s (2020) findings suggested that individuals experiencing
mental distress and their families would be more likely to have difficulty belonging and
fully participating in their faith community. Additionally, they would be less likely to
find adequate support in faith communities where church leaders and congregants
embraced spiritual explanations for mental distress. Congregants in these faith
communities may dismiss others’ mental distress experiences and withhold support from
them. Participating in such faith communities will make managing their mental health
challenges even more difficult for families of individuals with mental distress.
Lloyd and Waller’s (2020) study took place in England. The findings suggested
that beliefs about mental distress in the faith communities they surveyed were not as
stigmatizing as they were in similar studies. For example, Stanford (2007), conducted a
study in the United States over a decade ago. In that groundbreaking quantitative study,
Stanford assessed participants’ interactions within their faith communities. Specifically,
Stanford wanted to identify congregants’ attitudes toward fellow parishioners living with
mental distress. Approximately 58% (n = 170) of participants experienced mental
distress, while 42% (n = 123) lived with another family member’s mental distress. A total

of 293 Christians living in America, which comprised 226 Protestants, and 67 Catholics,
participated in the anonymous online survey.
Stanford (2007) found that 30% (n = 88) of participants encountered unpleasant
experiences within their church congregations. Fellow parishioners and clergy members
blamed family members or individuals living with mental distress or showed little interest
in understanding their mental health challenges. Besides feeling abandoned, fellow
parishioners deterred families or individuals experiencing mental distress from seeking
professional mental health treatment. Such responses to mental distress were
consequential for church participation and communal life. For example, Stanford noted
that 12.6% (n = 37) of family members or individuals living with mental distress left their
faith community, while 14.7% (n = 43) reported a weakened faith.
Lloyd and Waller (2020) noted a decline among Evangelical Christians endorsing
spiritual explanations for mental distress compared to similar studies conducted in the
United States several years prior (Stanford, 2007; Stanford & McAlister, 2008).
Unfortunately, Stanford’s (2007) study must be replicated in the United States to
determine what has changed regarding mental distress causation beliefs in Evangelical
faith communities. Still, Stanford and McAlister (2008), and Lloyd and Waller’s studies
supplied further evidence that causation beliefs in a faith community influence
congregants’ experiences of mental distress whether they are family members or the
individuals with the mental health conditions.

Although there were family members of individuals experiencing mental distress
in the study’s sample, Lloyd and Waller (2020) focused their study on participants’
experiences outside the family context. Lloyd and Waller opined that a phenomenological
exploration of British Evangelical Christians’ understanding of mental distress would
provide insight into how they make sense of their experiences. Indeed, a
phenomenological exploration can yield new information to inform mental health
professionals and clergy members’ responses to U.S. Evangelical Christians living with a
family member experiencing mental distress.
Christian Families’ Coping Experiences and Roles of Faith Communities
Religious coping refers to specific approaches to coping based on a person’s
belief system and faith practices. It plays a mediating role, protecting individuals and
helping them adjust to stressful life events because of their religious beliefs (Abu-Raiya
& Pargament, 2015; Pargament et al., 1998). Religious coping can help individuals find
meaning and comfort in their nearness to God, maintain control, and be closer to church
leaders and fellow congregants. Additionally, religious coping facilitates the
transformation of people’s lives, enabling them to transition from their current difficult
life circumstances, make changes, and embrace a new direction (Pargament, 2002). The
literature on religious coping suggests that Christians tend to rely on informal social
relationships in their faith communities in times of distress, namely, the relationships
with church leaders and fellow congregants for support (Krause et al., 2001; Krause &
Hayward, 2012b; Nooney & Woodrum, 2002). Indeed, Krause (2016) and Krause and

Ironson (2019) found that regular church attendance correlated with greater emotional
and spiritual support from other church members.
Pearce et al. (2016) examined the role of religious coping strategies in individuals
living with a family member experiencing mental distress. They wanted to determine if
there was a relationship between family members’ religious coping and mental health
services utilization. A total of 436 individuals representing parents, siblings, and spouses
of individuals experiencing mental distress participated in the study. The recruitment of
participants occurred over more than 3 years, and Pearce et al. used multiple assessment
measures to assess participants’ coping strategies, caregiving experiences, mental distress
burden, family functioning, and participation in counseling and support services.
Findings from Pearce et al.’s (2016) study demonstrated that religious coping
strategies played a moderating role in individuals living with a family member
experiencing mental distress. These individuals reported more meaningful caregiving
experiences. Pearce et al. credited participants’ adaptive responses to their religious
beliefs and support from their faith communities; however, the more the participants
endorsed religious coping strategies, the more they discarded other forms of coping and
assistance outside their faith communities, with detrimental consequences to them and
their family members experiencing mental distress (Pearce et al., 2016). For instance,
participants who resorted to spiritual coping strategies to manage their family members’
mental distress experienced higher caregiver burden, had inadequate mental health
literacy, and the beneficiaries of their care fared worse (Pearce et al., 2016).

Collaboration between faith and professional mental health communities can
benefit caregivers and their family members experiencing mental distress. A faith
community is an essential resource for family members to cope with another member’s
mental distress; thus, when faith communities fulfill their supporting roles, they are
invaluable sources of strength and encouragement. Exploring their roles in the lives of the
prospective participants of my study is relevant and imperative to understand and
describe the totality of their experiences with a family member’s mental distress.
Pearce et al. (2016) provided valuable information about Christians’ coping
preferences living with a family member’s mental health experiences, especially when
they endorsed religious coping strategies. The researchers did not investigate the types of
religious beliefs, denominations of the faith communities, and spiritual coping families of
individuals living with a member’s mental distress used in their study. Also, they did not
explore how the faith communities supported the family members of the individual
experiencing mental distress.
Practical Resources in Faith Communities’ Roles for Mental Distress
Increasingly, Christians have endorsed diverse views about mental distress that
include spiritual, psychological, and biomedical explanations (Lloyd & Waller, 2020;
Payne & Hays, 2016; Santos & Kalibatseva, 2019; Stanford & Philpott, 2011). Despite
these changes in perceptions about mental distress, clergy members and congregants
struggled to support and provide practical resources for individuals and families living

with mental distress (Baldwin & Poje, 2020; Rogers et al., 2012; Stetz et al., 2011; Wong
et al., 2018).
The resources faith leaders offered to meet their congregants’ mental health needs
differed from one faith community to another, often based on several identifiable factors.
For example, some clergy members elected to fund congregants’ mental health services
outside of the faith communities for practical reasons. First, the faith leaders
acknowledged that some congregants’ mental health needs were beyond their ability
adequately to address them. Also, providing monetary assistance to congregants for
mental health counseling removed the financial barrier that would otherwise prevent
them from receiving support services. Finally, when congregants participated in
confidential mental health services outside of the faith community, they avoided the
potential stigma of mental distress in their churches (Csiernik et al., 2020).
Some clergy members preferred church-based peer support groups (Hankerson et
al., 2013; Rogers & Stanford, 2015), and others have developed counseling programs or
ministries to support families and individuals living with mental distress (Brinkley &
Kaul, 2014; Stetz et al., 2011; Sullivan et al., 2014). Often, the choice to provide mental
health resources rested on the theology and biblical teachings in the faith community.
Also, referrals to outside mental health providers depended on faith leaders and
professional mental health counselors’ ability to establish mutual trust (Baldwin & Poje,
2020; Sullivan et al., 2014).

Mental Health Programming
Bornsheuer et al. (2012) explored conservative Protestants’ perceptions of mental
health programming in their faith communities and their preferred types of support
services. The researchers used descriptive phenomenology to answer two research
questions. The first question pertained to evaluating respondents’ perceptions of the
mental health care available to them in their respective faith communities. The second
question concerned church members’ views on the accessibility of the mental health care
available in their faith communities.
Altogether, 14 Christians, including church members and pastors from
Evangelical Baptist, Southern Baptist, Church of Christ, and Lutheran churches,
participated in the study. First, participants answered a demographic questionnaire and
four short-answer questions about mental health programming in their faith community.
Secondly, they participated in a semistructured interview about their perceptions of
mental health care. Afterward, Bornsheuer et al. (2012) used Moustakas’ (1994) modified
version of the Stevick–Colaizzi–Keen method to analyze the data they collected and
describe the meaning of participants’ experiences in their faith communities.
Bornsheuer et al.’s (2012) findings suggested that participants overwhelmingly
preferred faith communities as the primary resource for congregants in need of mental
health care. The participants credited their relationships with church leaders and fellow
congregants for their well-being. They indicated that people in their congregations had

their best interests at heart. The participants experienced acceptance and support in a faith
community with shared values and beliefs.
Regarding the perception of mental health services, Bornsheuer et al. (2012)
found that participants preferred skilled counselors to provide mental health care to
congregants. The participants believed the mental health services were most beneficial
when spiritual practices such as prayer and scripture reading were a part of the care they
received. To congregants, such an integration symbolized respect for their worldviews
and how their religious values contributed to their mental health. Concerning accessibility
of the mental health services, participants indicated that individuals in the faith
communities might be uninformed about existing resources to support their mental health
needs (Bornsheuer et al., 2012); consequently, they suggested the church promoted its
mental health services to congregants (Bornsheuer et al., 2012).
Bornsheuer et al.’s (2012) findings showed that congregants valued not only the
relationships with their faith leaders and fellow congregants they also preferred seeking
mental health assistance from their faith communities. They wanted mental health
services that were compatible with their faith convictions; thus, exploring prospective
participants’ relationships within their faith communities may prove to be an essential
contributing element in understanding to a fuller extent the experiences with their family
members’ mental distress.
Bornsheuer et al. (2012) used descriptive phenomenology for their study. Their
findings suggested that participants preferred a community in which people cared for

each other and where mental health services were available to families and individuals
living with mental distress. Such an environment positively impacts the daily experiences
of how individuals and those who care for them experience mental distress; however, the
researchers did not explore the research participants’ mental health concerns or needs.
Additionally, they did not describe what mental health needs the support services in the
faith communities addressed.
Wesselmann et al. (2015) investigated how individuals’ religious beliefs about
mental distress influence the nature of the social support they were willing to give to
people experiencing mental distress. A total of 164 Purdue University students
participated in the study, comprising 60 Roman Catholics, three orthodox Christians, two
Black Protestants, 78 Evangelicals, and 21 mainstream Protestants. The researchers
collected information from participants over two semesters and measured their mental
distress beliefs. Then the researchers presented participants with a scenario prompting
them to decide on the type of social support, either secular or spiritual support, to offer a
friend living with depression. The findings suggested that Evangelical Christians were
more likely to attribute spiritual causes to mental distress compared to mainstream
Protestant and Roman Catholic Christians in the sample. Evangelical Christians also
favored giving spiritual support to individuals experiencing mental distress. They
preferred a spiritual response to a spiritual problem.
Wesselmann et al.’s (2015) findings substantiate the idea that people’s religious
beliefs are a fundamental factor mediating how they make sense of mental distress and

respond to it, namely the nature of the social support they offer. This finding further
corroborated that congregants and church leaders in faith communities struggle to grasp
individuals’ experiences of mental distress. Endorsement of spiritually based
explanations for the causes and treatment of mental distress informed people’s preference
for the spiritually based support they offer (Wesselmann et al., 2015). Wesselmann et
al.’s study offered readers an insight into the thought processes that could inform
Evangelical Christians’ social support preferences for individuals with mental distress
experiences. Nonetheless, since the study’s setting was not in a faith community, the
findings may not provide a complete explanation for the lack of support family members
of individuals with mental distress face in Evangelical faith communities.
Scholars who studied the topic of mental distress and Evangelical Christians in
their faith communities underscored an overwhelming need for Christian faith
communities to collaborate with professional mental health service providers (Baldwin &
Poje, 2020; Rogers et al., 2012; Stanford & Philpott, 2011; Sullivan et al., 2014). Among
other things, they suggested that such a collaboration would increase faith leaders’ mental
health literacy and support them in attending to parishioners’ mental health needs. Also
evident in the literature was that many church leaders were influential decision-makers
regarding ways to address mental health needs in their faith communities. Whatever
course of action they pursued, whether to be a healing community for families and
individuals living with mental distress, use or refrain from using professional mental
health counselors, those choices impacted how congregants experienced mental distress

(Baldwin & Poje, 2020; Hodge et al., 2020; Sullivan et al., 2014).
Selected Phenomenological Studies
Below, I present a critical review of a few phenomenological studies about mental
distress. I selected these studies based on their relevancy to my dissertation topic and the
research method I used. I begin with a study that focused on the lived experiences of
Christians living with chronic illnesses in a Catholic faith community, followed by a
study about religious coping experiences of African American Christian women. My last
study focuses on families’ experiences with mental distress stigma.
Dyess and Chase (2010) conducted a phenomenological study in 2008 within a
U.S. Catholic faith community. Their research goal was to discover the essence of
participants’ lived experiences with chronic health conditions. The researchers wanted to
uncover the meaning of living with a chronic illness while being active participants in a
faith community. The research participants were four men and four women between the
ages of 69 to 91. They were active in their Catholic faith and participation in the life of
their church. All participants had one or more chronic illnesses, including heart disease,
diabetes, arthritis, depression, osteoporosis, or cancer. Additionally, they were fluent in
English and lived with one or more chronic illnesses for at least 3 months. Lastly, the
study respondents participated in the faith community nursing program on their church
campus daily or weekly.
Dyess and Chase (2010) recruited participants during a church event. The
researchers used a purposive sample to select participants in the study. After the

recruitment process, participants completed a health survey, then took part in
semistructured and open interviews. Dyess and Chase transcribed the data and analyzed
them using van Manen’s interpretive phenomenological approach. The researchers also
analyzed health surveys, field notes, and relevant artifacts.
The central theme from Dyess and Chase’s (2010) study was living in abundance.
This central theme was the outcome of two subthemes: (a) caring relationships in the
community of faith and (b) thriving from caring while living with chronic illness in the
community. Living in abundance encapsulated participants’ experiences of living
fulfilled lives rooted in enjoying their relationship with God and others while managing
chronic health problems. The findings showed that participants did not dwell on their
chronic illnesses. Instead, they embraced the goodness of God that they experienced in
caring relationships, first with God, then with the members of their faith community, and
finally with the greater community. According to Dyess and Chase, participants gained
new perspectives about living by caring for people around them. Caring for others has
become a way of life, providing participants with a renewed purpose. So, by adjusting
their lives and shifting their priorities, participants transcended the daily discomfort of
living with chronic health conditions and focusing on things greater than themselves.
Although the participants in Dyess and Chase’s (2010) study had difficult medical
health conditions, their involvement in a community of people with shared similar values
was instrumental in their lived experiences. As Dyess and Chase concluded, faith
communities are venues where a person can find caring social and spiritual support.

Dyess and Chase’s research showed that participation in faith communities could make a
positive difference in the lived experiences of individuals living with adverse health
conditions. Moreover, Dyess and Chase’s study demonstrated that individuals living
with life-debilitating conditions could still thrive and find fulfillment if they had access
to appropriate support and health services.
Dyess and Chase (2010) used a phenomenological approach to explore
individuals’ experiences of living with a chronic illness in a faith community. Using a
hermeneutic phenomenological method, Dyess and Chase unveiled how participants
interpreted and assigned meaning to their experiences of living with a chronic illness.
Another contribution of the study was the researchers showing the positive influence of
participants’ religious beliefs and their active membership in a faith community on their
experiences of living with chronic illnesses. Overall, the findings from Dyess and
Chase’s study underscored the moderating role of religious beliefs, participation in the
faith community, and caring relationships within a faith community in helping a person
living with adverse health conditions adjust and improve functioning.
My research will be different from Dyess and Chase’s (2010) study in the
following ways. First, the focus of my research will be exclusively on mental distress and
not any chronic illnesses. Secondly, my study setting will be in an Evangelical faith
community and not a Catholic faith community. So, prospective participants will be
Evangelical Christians who practice their religious beliefs and are active participants in
their church’s life. Thirdly, unlike in Dyess and Chase’s study, prospective participants

will be family members of individuals experiencing mental distress. Lastly, I will use
descriptive and not hermeneutic phenomenology because my goal is to explore and
describe participants’ day-to-day experiences of living with the mental distress of a
family member.
Harris et al. (2019) conducted a phenomenological study to explore the role of
religious coping in mental health, specifically African American Christians’ religious
coping preferences. The researchers recruited the study’s participants through purposive
and snowball sampling techniques. Seven married and single African American women,
aged 26 to 58, responded to social media postings, emails, or invitations. All the
participants were Christians, including Protestants, Pentecostals, and Evangelicals.
The participants answered a demographic questionnaire and a semistructured
interview to furnish data for the study. For data analysis, Harris et al. (2019) used
Moustakas’ (1994) modified version of van Kaam phenomenological method. Before
proceeding with the data analysis, the researchers bracketed their experiences. Also, they
used member checking and an independent auditor to ensure the themes they identified
were consistent and reflected the research participants’ views and experiences.
Harris et al. (2019) identified six themes from the data analysis, which are as
follows: (a) God is a keeper: getting through the “valley,” (b) positive religious coping,
(c) negative religious coping, (d) spiritual growth, (e) “godly counsel” and “sound
doctrine,” and (f) “Black people do not go to counseling” (p. 176). Together, these
themes underscored essential elements in the religious coping experiences of the research

participants. First, participants credited God as the reason for their ability to maintain
their mental health. The participants viewed their faith community as an extension of
God's presence in their lives and a place to develop meaningful relationships.
Secondly, the study’s results revealed that participants used both positive and
negative religious coping. At times, participants questioned God and expressed doubt
about God’s involvement in their lives. At other times, they read their Bible for guidance,
prayed, and sought comfort and social support from fellow congregants. Thirdly, Harris
et al.’s (2019) findings showed the role of a person’s religious beliefs in the
meaningmaking process. Participants used their religious beliefs and coping practices to
make sense of their experiences. Lastly, Harris et al.’s findings highlighted the effects of
mental distress stigma on participants, resulting in their distrust of mental health
counseling.
Harris et al. (2019) demonstrated that a person’s religious copings are essential to
their mental health. The study’s participants credited their religious beliefs, spiritual
practices, and faith community for their mental health. For instance, this study’s
participants’ relationship with God was determinant in maintaining their mental health.
Furthermore, the study findings suggested that certain religious coping practices might
resonate more with some Christians, depending on their cultural backgrounds or past
personal history. For example, while many participants relied on their faith community
for support, others avoided seeking help from within their faith community because of
past traumatic experiences in the church.

For Christians, such as Evangelicals, who believe in a personal relationship with
God, understanding their concept of who God is and their views about God’s place in
their lives is critical to understanding their mental health experiences. As Harris et al.
(2019) showed, faith communities can be a dreadful place for some Christians or a place
of healing and solace for others. These findings will inform how I collect data for my
study about prospective participants’ involvement with their faith communities.
Exploring the extent to which the study’s participants rely on their faith community for
support may yield helpful information about their daily lived experiences with their
family member’s mental distress.
Harris et al.’s (2019) choice of a phenomenological research method to describe
religious coping experiences allowed them to develop themes pointing to the significance
of religion and spirituality (i.e., faith, God, Bible, and the faith community) in the lives of
the research participants. While these findings were informative in understanding the
essence of participants’ religious coping experiences and assisting both faith leaders and
mental health professionals in providing support services, their transferability will be
quite limited due to the study sample. In this study, participants were exclusively women.
The participants were also highly educated, with their earnings higher than the average
income for African American women.
Eaton et al. (2016) used a qualitative research method to examine and describe
how parents of children with emotional and behavioral disorders experienced self-stigma.
They used a convenience sample to recruit 14 Australian biological parents of children

living with mental distress, including anxiety disorder and oppositional defiant disorder.
Following the recruitment, Eaton et al. created a participatory action research group
consisting of four parents of children with emotional and behavioral disorders. The goal
for the participatory action research group members was to ensure a sensitive and
respectful study that reflected participants’ experiences. Throughout the research process,
Eaton et al. solicited feedback from the group members who were actively involved in
reviewing the research process, including the interview questions and the research
question, which was as follows: “How do parents of children with mental health disorders
experience self-stigma?”
Altogether, Eaton et al. (2016) conducted 12 semistructured interviews but
focused their analysis on the experiences and perspectives of the 11 mothers, excluding
the only male participant. The researchers used Giorgi’s (2009) descriptive qualitative
method to analyze their data. They identified five themes: (a) the good parent ideal, (b)
awareness of external stigma, (c) outcomes of external stigma, (d) internalizing stigma
and self-doubt as self-stigma, and (e) refuting self-stigma.
Eaton et al. (2016) found that all participants reported self-stigma due to the
public mental distress stigma they experienced. Participants described self-stigma as an
impairment to their self-esteem, self-efficacy, and personal well-being. They viewed
themselves as failed parents and doubted their ability to parent competently. In light of
their findings, Eaton et al. remarked that participants viewed themselves as failures, an

essential characteristic of self-stigma. Participants who confronted their self-stigma
seemed to mitigate its worst effects.
The findings from Eaton et al.’s (2016) study suggested that family members of
individuals with mental distress could internalize public stigma. The study’s results also
showed that the effects of living with another person’s mental distress go beyond public
mental illness stigma. For instance, a child’s mental distress had adverse consequences
for the study’s participants, such as confronting negative self-concept and damaged
selfefficacy. While the researchers did not suggest that all family members living with
another member’s mental distress would experience a negative self-view, the finding is
relevant for my study. For example, exploring how the participants in this current study,
who self-identified as Evangelical Christians, viewed themselves due to living with a
family member experiencing mental distress could reveal pertinent information about
their daily lived experiences.
Eaton et al. (2016) used Giorgi’s (2009) phenomenological research method,
highlighting participants’ perspectives and not the researchers’ views about the
phenomenon under study. Furthermore, the researchers’ use of a participatory action
research group was an extra measure that guaranteed respect and sensitivity to
participants’ stories. Eaton et al. chose not to determine parental mental health status
prior to the study. As they acknowledged, there was a possibility that parental mental
distress and subsequent stigma could have interfered with how they experienced the
stigma related to their children’s mental health conditions.

Conversations about mental distress within Christian faith communities in the
scholarly literature comprised of various themes and interests, including defining and
explaining the causes of mental distress, religious coping and treatment approaches,
clergy members’ roles in addressing the effects of mental distress in faith communities,
and collaboration between clergy members and mental health professionals (see Baldwin
& Poje, 2020; Freeman & Baldwin, 2020; Hodge et al., 2020; McGuire & Pace, 2018).
The extant literature pointed to a tendency in believers to explain mental distress from a
religious perspective within Evangelical Christianity, fostering stigma (see Freeman &
Baldwin, 2020; McGuire & Pace, 2018; Peteet, 2019; Stanford, 2007; Stetz et al., 2011;
Webb, 2012; Webb et al., 2008; Wesselmann & Graziano, 2010). Clergy members and
congregants seemed to either ignore or remain silent on mental distress issues in their
midst, resulting ultimately in faith communities offering little support to individuals and
families living with mental distress (see Abraham, 2014; Rogers et al., 2012; Stetz et al.,
2011; Wong et al., 2018).
There is sufficient evidence in the literature that inadequate mental health literacy
among clergy members and their distrust of mental health can explain their attitudes
toward mental distress and the lack of supportive services available in faith communities
(see Anthony et al., 2015; Bledsoe et al., 2013; Hodge et al., 2020; Jang et al., 2017;
Jones et al., 2012; Vermaas et al., 2017). Scholars have been advocating for better
collaboration between clergy members and mental health professionals to meet the
mental health needs in faith communities (see Baldwin & Poje, 2020; Rogers et al., 2012;

Stanford & Philpott, 2011). However, the lack of trust between these two groups,
representing two different ideologies, has been a significant obstacle to sustainable
collaborative relationships (see Baldwin & Poje, 2020; Hodge et al., 2020; Sullivan et al.,
2014).
Summary
Explanations for mental distress within Christianity are on a continuum, ranging
from biomedical and psychological to religious causation beliefs (see Freeman &
Baldwin, 2020; Hodge et al., 2020; Lloyd & Waller, 2020; Payne & Hays, 2016; Santos
& Kalibatseva, 2019; Stanford & Philpott, 2011). Mental distress remains a concern in
faith communities as clergy members struggle to address its effects and meet
congregants’ mental health needs (see Baldwin & Poje, 2020; Hodge et al., 2020; Rogers
et al., 2012; Sullivan et al., 2014). The varying beliefs and attitudes toward mental
distress within Christian faith communities affect the experiences of congregants
regarding the social support and mental health resources available to them (Adams et al.,
2018; Freeman & Baldwin, 2020; Jones et al., 2012; Lefevor et al., 2020; Sullivan et al.,
2014; Wesselmann et al., 2015). While mental health resources exist outside of faith
communities, many Christians often distrust professional mental health counseling and
prefer counseling and mental health resources compatible with their faith, values, and
culture (see Cragun & Friedlander, 2012; Harris et al., 2019). Mental health professionals
continue to show little interest in valuing and respecting Christians’ religious beliefs in
counseling (Harris et al., 2016).

Although Evangelical Christians represent a sizeable portion of Christians in the
United States (Gallup, n.d.), there is little in the extant literature describing their lived
experiences with mental distress. Such a knowledge gap does not help mental health
professionals and church leaders provide adequate resources to meet family members’
mental health needs. My study will help fill the gap by describing Evangelical Christians’
daily lived experiences living with the mental distress of a family member. In Chapter 3,
I will explain my research method framework. I will also discuss my position and role in
the research study and address other relevant matters.
Chapter 3: Research Method
I conducted a qualitative study to explore and describe Evangelical Christians’
daily living experiences with a family member’s mental health challenges through the
lens of their religious beliefs and life in their respective faith communities. In this
chapter, I describe transcendental phenomenology, the chosen research approach to
answer the research question. The chapter contains discussions of my role as the
researcher, the research participant selection, and the data collection and data analysis
processes. Throughout the chapter, I also review my responsibilities in conducting an
ethical study and address concerns about the study’s trustworthiness.
Research Design and Rationale
The study’s primary research question was: How do Evangelical Christians
describe their day-to-day life with a family member experiencing mental distress?

Additionally, I designed two subquestions to inform my interviews and support a
comprehensive and meticulous exploration of participants’ experiences in everyday life
(see Creswell & Creswell, 2018; Englander, 2020). The subquestions were: (a) How do
Evangelical Christians living with a family member experiencing mental health
conditions view mental distress? and (b) What are Evangelical Christians’ perceptions of
their faith community’s responses to their day-to-day life with a family member
experiencing mental distress?
As a qualitative researcher, I could have explored the topic under study using
various research designs. For instance, with a case study design, I could have collected
data through interviews and participants’ observations to attain an in-depth understanding
of the phenomenon I wanted to describe. However, as a research design, a case study is
more appropriate for a real-life context case or for comparing multiple events within a
specific time and place (see Creswell & Poth, 2016; Patton, 2015). I also could have used
the grounded theory design, which would have allowed me to build a theory or
framework to explain participants’ experiences of living with a family member with
mental distress (see Creswell & Creswell, 2018; Creswell & Poth, 2016). However, the
nature of the research problem, the research question, and the knowledge I was seeking
guided my design selection. The knowledge I sought to discover was about the essence of
participants’ experiences of another person’s mental distress. My focus was on the
subjective nature of participants’ experiences and the contexts in which they lived and

assigned meaning to their experiences (see Ravitch & Carl, 2016). To that end,
phenomenology was the most appropriate research design for this study.
Specifically, I used transcendental phenomenology to explore Evangelical
Christians’ day-to-day experiences of living with a family member with mental distress.
Phenomenology is both a philosophy and a method with a singular focus, namely,
consciousness (Giorgi, 2009, 2012). It seeks to understand the qualities and activities of
consciousness, such as how an object or phenomenon appears to a person’s consciousness
(Giorgi, 2009, 2012). Husserl theorized that consciousness mediated people’s interactions
with the world around them, thus making phenomenology the ideal research method to
discover knowledge, in this case, exploring individuals’ experiences of living with
another person’s mental health challenges (see Giorgi, 2012; Moustakas,
1994).
Although phenomenology originated with Edmund Husserl, there are two main
phenomenological traditions. The first tradition is transcendental phenomenology, which
is descriptive and aligned with Husserl’s philosophy. The second tradition represents
Heideggerian phenomenology and is interpretive (Giorgi, 1997). Researchers using
Heidegger’s phenomenology explain and interpret the phenomenon they are studying,
often embracing external sources of knowledge or theories that do not emanate from
participants’ narratives. In contrast, researchers who adopt Husserl’s phenomenology do
not depart from participants’ descriptions of their experiences. Rather than explain or
interpret, transcendental phenomenologists use language to articulate what is given (i.e.,
their intuition from participants’ accounts; Giorgi, 1997, 2012).

I selected transcendental phenomenology to provide the framework for my study
to understand better Evangelical Christians’ experiences of living with a family member
with mental distress. My goal was to accurately describe the essential features and
meanings present in participants’ narratives of their experiences (see Qutoshi, 2018). As
such, I put aside any preconceived knowledge about mental distress and past experiences
and focused on participants’ experiences (see Giorgi et al., 2017; Moustakas, 1994). By
assuming the phenomenological reduction attitude, which consists of withholding
previous knowledge and judgment to grasp the phenomenon as the participants describe
it, I gained insight into participants’ perspectives and used language to describe the
structures and meaning of their experiences (see Giorgi, 2012).
Role of the Researcher
As a qualitative researcher, my interest was to understand how the research
participants experience a phenomenon and give meaning to the daily realities and
circumstances they live through (see Denzin & Lincoln, 2013; Ravitch & Carl, 2016). I
was aware that my interactions with the research participants were not neutral since I was
a participant-observer. In this position, I was fully present to the participants’ world,
listening and journeying alongside them to discover the meaning of their lived
experiences as they shared them (see Englander, 2020). My socio-cultural background,
values, and behaviors, including my presence, also influenced the research process, from
the study design to the interview process to data analysis and the reporting of findings
(see Bourke, 2014; Karagiozis, 2018). Therefore, as the primary data collection

instrument in this study, I was cognizant of my impact on the different stages of the
research process, including my views, biases, and motivation for conducting the study
(see Bourke, 2014; Giorgi, 2009). For example, I used journaling to maintain awareness
of my thought processes about the phenomenon to remain as objective as possible (see
Peoples, 2020).
My objective was to obtain detailed accounts from participants to understand and
accurately describe the essential features of their lived experiences (see Giorgi, 2009);
hence, I listened to participants’ stories, namely, what it was like living with a family
member who experienced mental distress, how they lived through the day-to-day
circumstances, and how they made sense of their experiences (see Giorgi, 2009;
Neubauer et al., 2019). Throughout the data collection process, I protected participants’
autonomy and safety by refraining from asking questions that would cause undue stress
or trick them into providing information they were uncomfortable sharing (see ACA,
2014; Ravitch & Carl, 2016).
During data analysis, I assumed the phenomenological attitude, continually
assessing and putting aside my preunderstanding of the phenomenon that could prevent
access to participants’ narratives. I accepted participants’ accounts as reflecting the
phenomenon under study as manifested to their consciousness (see Giorgi, 2009). I also
paid attention to features buried in participants’ stories and hidden from their awareness,
although present in the descriptions of their daily experiences. These features comprised

daily routines, situations they considered mundane, or events they deemed irrelevant and
might have taken for granted (see Englander, 2020; Giorgi, 2009; Neubauer et al., 2019).
In all, I had predetermined knowledge about mental distress. I also entertained
hopes that the study findings would raise the awareness of mental health challenges in
churches and perhaps contribute to changing how mental health professionals,
congregants, and church leaders view and address mental distress needs. On a
professional level, I am a mental health counselor with years of experience working with
individuals and families living with mental distress. Through my professional experience,
I have gained expert knowledge about mental distress that could have interfered with my
ability to remain focused on participants’ experiences. On a personal level, I am a
professed Christian with religious beliefs similar to those of the research participants. I
had an interest in seeing Evangelical Christians benefit from mental health services.
Furthermore, I desired to see a growing acceptance of mental distress in faith
communities, which I believed might bolster faith leaders’ effectiveness to attend more
efficiently to the needs of those living with mental distress.
To mitigate these potential risks of bias, I disclosed my motivation for conducting
the study to the research participants (see Bourke, 2014). Next, I engaged in bracketing to
deepen my awareness of my worldviews, values, and beliefs and examine their potential
impact on this research project (see Rolls & Relf, 2006). I also kept a reflective journal
about my experiences throughout the research process, documenting and monitoring how

my background experiences affected the overall study and recording my impressions after
each interview (see Brinkmann & Kvale, 2018; Creswell & Creswell, 2018; Rolls &
Relf, 2006; Vicary et al., 2017).
I took steps to maintain cordial but professional interactions with the research
participants. I respected the rights of research participants to remain anonymous and
safeguarded the confidentiality of the data they provided, removing information that may
compromise their identity (see Ravitch & Carl, 2016). Participants were presented with a
clear and detailed written informed consent form that explained the research purpose, the
data collection process, and my plan to store their information safely. The potential risks
and benefits of participating in the study were explained, including confidentiality and
privacy concerns. I also informed participants about the dissemination strategy of
research findings (see ACA, 2014). Individuals with whom I had a past, or existing social
or professional relationship were not included in the study. MacDonald and Greggans
(2008) believed that informed consent to participate in a study also included access to the
privacy and physical space in participants’ homes. Therefore, I provided all the necessary
information to the research participants for them to make an informed choice to protect
their privacy and rights (see Coughlan & Cronin, 2009).
Lastly, power issues could have arisen during data collection (see ACA, 2014). In
the interviewer-interviewee relationship, I might have appeared as a person of influence,
an expert on the subject matter; however, I understood that the interviewer-interviewee
relationship was not hierarchical but a “we-relationship” in which we explored their lived

experiences together (see Englander, 2020, p. 62). Accordingly, I refrained from doubting
or disputing participants’ accounts (see Giorgi, 2009; Nunkoosing, 2005).
Methodology
The phenomenon I explored in this study was Evangelical Christians’ experience
living with a family member with mental distress. In this section, I explain the procedures
followed in conducting this qualitative research study. Together, these steps and
processes, including participant selection, data collection, and data analysis, allowed me
to answer the research questions.
Participant Selection
Participants identified with Evangelical Christianism and were active in their faith
and active members of their faith communities. A perfect number of participants for
phenomenological studies does not exist (Patton, 2015); however, I initially planned to
recruit six to 10 Evangelical Christians for this phenomenological study. Qualitative
research scholars such as Creswell and Creswell (2018) estimated that three to 10
participants constituted an appropriate sample size. Guest et al. (2006) suggested have no
more than 12 participants, and Giorgi (2009) estimated three participants were adequate
in a phenomenological study. Furthermore, a brief review of recent researchers who
conducted descriptive phenomenological studies used a sample size of participants that
ranged from five to 11 individuals. For example, Morley et al.’s (2015) had five nurse
participants in the phenomenological study to explore their experiences working with
patients with substance use disorders. Armour-Burton and Etland (2020) recruited 10

African American women with breast cancer to research participants’ well-being. Lastly,
Eaton et al. (2016) interviewed 11 mothers to study self-stigma in parents living with
their children’s mental distress.
The justification for a small sample size of participants in phenomenological
studies is that it affords qualitative researchers the opportunity to focus on the essential
structures of the phenomenon under investigation (Englander, 2012). As is customary in
qualitative research, I also used data saturation to determine my final sample size (see
Shelton & Bridges, 2019). Data saturation occurs when the researchers deem no fresh
insights are coming from their data and discontinue interviewing new research
participants (Creswell & Creswell, 2018; Guest et al., 2006; Saunders et al., 2018).
I used purposive sampling to select participants familiar with the phenomenon
under study and who met some specific criteria representing the population of interest in
the study (see Battaglia, 2008; Gill, 2020). A purposeful sampling strategy allowed me to
be selective and recruit only participants with rich enough information to answer the
study’s research questions and purpose (see Patton, 2015). Additionally, I used snowball
sampling to generate additional participants who met my selection criteria through
current research participants (see Crouse & Lowe, 2018).
I located research participants by contacting professional counselors and directors
of counseling centers servicing Evangelical Christians. Support groups for families of
individuals with mental health challenges, such as Grace Groups in faith communities or
local chapters of the National Alliance on Mental Illness, were also sources for

participants. I also attempted to recruit participants through advertisements on social
media by posting a recruitment flyer (see Appendix A) that briefly described the research
project’s purpose and included my contact information. Prospective research participants
had to meet the following criteria to be included in the study: (a) Evangelical Christians
who are active in their faith, (b) be at least 18 years or older and currently living with, or
have lived with, a family member’s mental distress for at least 1 year, (c) the family
member experiencing mental distress must be formally diagnosed with any mental
distress, and (d) participants must be able to provide accurate descriptions of the
phenomenon I was interested in exploring (see Englander, 2012; Giorgi, 2009). I offered
all participants a $10 gift card and a short note of appreciation to express my gratitude for
their time and involvement.
Data Collection
I organized the data collection process, designed the interview questions, and
interviewed prospective participants. As Giorgi (2009) suggested, my goal was to obtain
descriptions that reflected the phenomenon as it appeared to participants’ consciousness.
For phenomenological studies, in-depth interviewing is the preferred instrument for
collecting detailed accounts from participants and understanding the phenomenon from
their perspectives (Patton, 2015; Rubin & Rubin, 2012; Shelton & Bridges, 2019).
After my initial contact with the prospective participants in which I introduced
myself and the research project in more detail, I sent respondents the screening
questionnaire (see Appendix B) to ensure they met the research participation criteria.

Next, I sent the written informed consent form (see Appendix C) to qualified individuals
via email and, in the same correspondence, invited them to offer dates, times, and places
for an eventual interview. Before the scheduled interview, demographic information (see
Appendix D) was obtained about the prospective participants. I allocated 90 minutes to
prepare for the interview with each participant to ensure I had adequate time to organize
and address unexpected technical challenges (see Morgan, 2011).
I kindly suggested virtual interviews using a secure online videoconferencing
platform such as Skype or Zoom to ease participants’ concerns during these times of
COVID-19 health crisis. I also offered phone interviews to accommodate participants’
needs and concerns as their circumstances demanded (see Creswell & Creswell, 2018).
The interviews were audio recorded (see Creswell & Creswell, 2018). I conducted one
face-to-face interview, but I practiced safety measures and social distancing guidelines,
such as wearing a face mask and maintaining a six-foot physical distance between myself
and the participant (see Centers for Disease Control and Prevention, 2020).
I followed the same interview guide with each participant, which began with an
introductory and closing script (see Appendix E). I started the interview with the
introductory script, which incorporated steps to establish rapport with the research
participants. Building rapport was essential for the success of the data collection process.
I was empathic and worked to create a trusting, nonjudgmental, and authentic atmosphere
for the interview (see Brinkmann & Kvale, 2018; Englander, 2020; Patton, 2015). Then, I
reviewed the purpose of the study, discussed the informed consent, and addressed

existing concerns about the participants’ involvement in the research, including privacy
and confidentiality (see Brinkmann & Kvale, 2018).
I followed the introduction with the interview, which lasted approximately 60
minutes. The length of each interview varied from one participant to another. While
Giorgi (2009) did not offer any specific recommendation about the interview’s duration,
he suggested that the phenomenon determined the interview length. Giorgi stated further
that an interview should not be too long or too short. Unnecessarily extended interviews
may lack focus, and extremely brief interviews may yield little insight into the
phenomenon under study (Giorgi, 2009).
I collected verbal data through one-on-one semistructured interviews with
participants (see Ravitch & Carl, 2016). I asked short and straightforward main questions
first, then follow-up questions for further clarification (see Brinkmann & Kvale, 2018).
The questions were broad and open-ended and gave participants the latitude to share as
much detail about their experiences as they wanted. I focused my questions on specific
life situations and encouraged respondents to describe their experiences as fully and
concretely as possible (see Giorgi, 1997, 2009). The goal of collecting data was to
discover the general knowledge and fundamental dimensions of what it meant to live with
another person experiencing mental distress (see Englander, 2012). I adapted
Bevan’s (2014) structure of phenomenological interviewing to develop the interview
protocol. Bevan suggested a structure that involves using the interview questions to assist
the interviewees in sharing their lived experiences in ways that give context to the lived

experiences, uncover specific details about their experiences, and clarify the meaning of
their experiences. I asked questions to encourage participants to describe specific
situations they experienced to reflect Giorgi’s (2009) recommendation for formulating
interview questions.
The closing script included a debriefing, which was completed after the interview.
During the debriefing, I shared some observations about the interview and gave
participants feedback (see Brinkmann & Kvale, 2018). I reviewed their interview
experience and overall involvement in the research process to ensure participation has
been beneficial to them (see Brinkmann & Kvale, 2018; Nelson et al., 2013).
Additionally, helpful resources were offered to participants who might need support,
including referrals for mental health counseling, self-help groups such as the NAMI
family support groups, and a list of self-care activities. Then, I thanked the participants
for their contribution to the research project. I asked permission from participants to
contact them later, if necessary, for follow-up interviews to clarify ambiguous statements
or complete missing information (see Giorgi, 2009).
Data Analysis
I used Giorgi’s descriptive phenomenological psychological method for data
analysis after transcribing participants’ descriptions of their lived experiences. I used
professional transcription services to transform the recorded interview into written text.
Then, I reviewed the transcribed texts, listening to the interviews’ audio recording again
to ensure the transcription accuracy (see Brinkmann & Kvale, 2018; Morris, 2015). Filler

words such as “um” or “like” were removed to enhance the transcripts’ readability and
comprehension, and I refrained from correcting the interviewee’s language to maintain
fidelity to participants’ narratives (see Brinkmann & Kvale, 2018; Morris, 2015). I also
avoided adding or filling any perceived gaps in participants’ reports and planned to solicit
a follow-up interview to gather any missing information or seek additional clarification
(see Giorgi, 2009). After transcribing the interviews, I sent each participant a copy of
their transcript to authenticate the accuracy of the report of what they shared during the
interview (see Birt et al., 2016; Peoples, 2020). The interview data were then analyzed
after completing the member checking processes (see Creswell & Creswell, 2018; Giorgi,
2009).
Giorgi’s descriptive phenomenological psychological method has five progressive
steps. To begin the analysis, I assumed the phenomenological attitude by bracketing any
beliefs or preunderstanding of the phenomenon so I could be present and listen attentively
to participants’ accounts of their lived experiences. In doing so, I captured and described
new knowledge about the phenomenon under study (see Giorgi, 2009, 2012). The first
step in the analysis was reading the entire data to get an overall sense of participants’
descriptions. I was sensitive to any implications in the narratives about what it meant to
live with another person experiencing mental distress; however, I refrained from
identifying themes or patterns based on the descriptions following the initial reading (see
Giorgi, 1997, 2009).

Secondly, I carefully read through the descriptions again, establishing meaning
units. A meaning unit represents shifts or transitions of meaning in the data; thus, I
identified and separated any such changes in meaning relevant to the phenomenon under
study (see Giorgi, 1997, 2012). As I constituted these meaning units, I avoided using any
predetermined criteria to establish them. The meaning units made the descriptions
manageable for data analysis (see Giorgi, 2009).
In the third step, I played a more active role as the researcher, using the process of
free imagination variation to determine the essential structures of the phenomenon (see
Giorgi, 2012). Free imagination refers to a natural method of discovering essences,
consisting of changing parts of a phenomenon to determine if that part is a fundamental
constituent of the phenomenon (Giorgi, 1997). I transformed participants’ descriptions
into explicit themes or expressions that bring forth their experiences’ psychological
features (see Giorgi, 2012). I reviewed the themes during the fourth step and connected
them to describe the phenomenon’s essential or general structure. In the fifth and final
step, I used the general structure I uncovered to make sense of the phenomenon in the
participants’ descriptions (see Giorgi, 2012).
Trustworthiness
Researchers ensure trustworthiness by demonstrating the credibility,
transferability, dependability, and confirmability of the study’s findings. Credibility
refers to furnishing evidence that the results of a study match participants’ views of their
experiences (Patton, 2015). Accurate reporting of the steps and strategies I used during

this study allows readers to evaluate the research process and findings. Moreover, they
can determine whether the results represent the participants’ descriptions of their
experiences (see Cope, 2014; Lincoln, 2004; Shenton, 2004). I also used member
checking by having the research participants review the study’s results to ensure their
accuracy. I sent them a summary of the themes that emerged from the accounts they
provided of living with a family member experiencing mental distress (see Creswell &
Creswell, 2018).
The transferability of a study’s results suggests the extent to which such findings
can fit or be applied to other research settings comparable to the original study (Shenton,
2004). To demonstrate transferability, I furnished information about my study’s settings
and methodology so that readers can determine how comparable my findings are to those
of studies done in similar contexts (see Lincoln, 2004; Shenton, 2004). As Giorgi (2009)
suggested, I described the method of analysis used in the study so that other researchers
can follow and critique the process to either affirm or reject the findings. Additionally, I
provided detailed descriptions of participants’ experiences so that future researchers can
establish how transferable are the study’s findings to other settings (see Korstjens &
Moser, 2018; Ravitch & Carl, 2016).
Dependability addresses consistency issues with the research process (Shenton,
2004). The dissertation committee members verified I followed the research approach,
design, and methods consistently, including the steps taken to recruit and interview
participants for data collection and analysis to ensure the study’s dependability (see

Creswell & Creswell, 2018). Lastly, confirmability requires that the study’s results reflect
participants’ descriptions of their experiences and not the researcher’s views (Patton,
2015; Shenton, 2004). Accordingly, the results of the study are not an explanation of the
phenomenon under exploration but the reporting of participants’ descriptions and
knowledge about the phenomenon (see Shelton & Bridges, 2019). I kept a reflective
journal to document the thought processes and steps I took to reduce researcher bias (see
Creswell & Creswell, 2018).
Ethical Procedures
Before the data collection activity began, I obtained approval from my
university’s institutional review board (IRB). My approval number was 05-27-
210566367. The IRB’s purpose is to ensure that researchers conduct safe studies for
participants, following research ethics and U.S. federal guidelines (Walden University,
2020). I recruited participants only after the approval from the IRB. Protection for
participants included respect for their rights and the privacy and confidentiality of their
information. Therefore, I took all the necessary steps to ensure that involvement in the
study did not harm participants.
Before the interview, I sent the informed consent to all qualified participants.
Participants had information about the research project in the package, such as the study’s
purpose and expectations for participating in the study. I provided participants with
information regarding the data collection process, the security of data, potential benefits
and risks associated with participation in the study, and their right to decline participation

at any time (ACA, 2014). I requested participants to review, sign, and return the included
informed consent. The signature indicated their approval of the steps I took to protect the
study’s integrity and the safety of all participants. Participants signed and indicated their
understanding and agreement to the informed consent terms by responding in an email
stating, “I consent.”
I took precautions to protect the identity of both the interviewee and the family
member experiencing mental distress. During the interview, I ensured that I was sensitive
to participants’ experiences, given the stigma surrounding mental distress. Also, talking
about a family member’s mental distress could unearth painful memories and emotions in
participants. I ensured that the interview questions focused on exploring the phenomenon
under study and did not intrude into participants’ private lives or pressure them to share
information that may violate their rights. Lastly, I provided participants with information
about available resources for mental health support services in their community, if
needed.
To maintain the confidentiality and privacy of the data I collected, I removed any
material that might contribute to participant identification. For example, I encrypted the
data using pseudonyms, then removed names and other contact information. I destroyed
all paper documents by shredding them and kept relevant encrypted data for the duration
stipulated in the informed consent. The encrypted data includes the analysis of the
interviews and the themes I developed (see Shelton & Bridges, 2019). I safeguarded the
audio recordings and other confidential records such as transcriptions and notes on a

password-protected portable storage device. These records and the portable storage
device are locked in a safe, and I will maintain them for 5 years. I am the only person
with access to the data, which I will delete after the specified duration.
Summary
I explained the choice of a phenomenological research design for the study in this
chapter. I reviewed my role in the research project and discussed the research
methodology, including an explanation of participant selection, sampling, and data
collection procedures. I also addressed trustworthiness and the steps I took to ensure that
the study findings accurately reflect participants’ descriptions. Lastly, I presented
additional measures I took to protect participants’ privacy and confidentiality of the data.
In Chapter 4, I will describe the study’s setting, participants’ demographics, the data I
collected for the study, and a data analysis report. I will end Chapter 4 by describing the
evidence of trustworthiness and presenting the results of the study.
Chapter 4: Results
The purpose of this qualitative phenomenological study was to explore and
describe Evangelical Christians’ everyday life with a family member who experienced
mental health challenges. I used in-depth interviewing to collect the participants’
accounts of their experiences through the lens of their religious beliefs and membership
in a faith community. Specifically, I explored the participants’ attitudes and perceptions
about mental distress, their sense of self and the family member experiencing mental
distress, and how they make meaning of their day-to-day experiences.

In this chapter, I describe the processes and strategies used to conduct this
research. I begin with the description of the conditions and settings of the interviews and
provide demographic information about the participants. The data collection and data
analysis procedures are explained before the study’s trustworthiness is established. Then,
I review the credibility, transferability, dependability, and confirmability of the study
results. Lastly, the study results are described and explained according to the themes
discovered.
Setting
I conducted eight semistructured interviews to collect data for this current
descriptive phenomenological study. The participants were interviewed individually and
joined the interviewing procedure via the videoconference platform, Zoom. Using the
videoconference platform allowed me to recruit participants from five different states,
widening and enriching the quality of the data collected. Except for one participant who
preferred a face-to-face interview, I conducted all other interviews from my private home
office via Zoom while the remaining participants joined me virtually from their homes.
Relying on this technology for data collection had its challenges. One such
challenge was a minor technical problem with the sound that occurred during the fourth
interview. Thankfully, the audio recording equipment functioned perfectly and captured
all the conversation details. Excluding that, I did not encounter any other circumstances
that would have prevented or distracted participants from sharing their experiences as
they wanted or that impacted the interpretation of the study findings.

Demographics
All eight participants self-identified as Evangelical Christians. Before sitting
down for the interview, they completed one screening document and one demographic
questionnaire (see Appendices B and D). Six of the participants were female, and two
were male, ranging from 46 to 68 years old. Most of the participants (n = 5) described
their experiences as parents living with a son or daughter’s mental distress, two
participants shared their experiences of living with a sibling’s mental distress, and one
participant shared her experiences involving a spouse’s mental health challenges. I
summarized each participant’s profile in the following subsections, using the
pseudonyms I assigned to them and their family member experiencing mental distress
after the interviews.
Adam
Adam is an adult, White male from the Midwestern region of the United States.
He is a Pentecostal Evangelical Christian. Adam is married with children. He described
his experiences living with his daughter, Adèle’s mental distress.
Ben
Ben is an adult, Asian male who resides in a Midwestern town in the United
States. He identifies as an Evangelical Christian and a former Presbyterian minister. Ben
shared his past experiences living with his younger sister, Barbara’s mental distress.

Claudia
Claudia is an adult, White female who lives in the Midwestern region of the
United States with an adult son, Christophe. Claudia is an Evangelical Christian and
attends a Christian Reformed Church. She described her experiences of living with
Christophe’s mental distress.
Deborah
Deborah is an adult, Asian female who identified as a Pentecostal Evangelical
Christian. Deborah lives in the Midwestern region of the United States and shared her
experiences of living with the mental distress of her sister, Danielle.
Elizabeth
Elizabeth is an adult, White female who resides in the Midwestern region in the
United States. Elizabeth is an Evangelical Christian and attends a nondenominational
church. She described her experiences of living with her husband, Edouard’s mental
distress.
Faith
Faith is an adult, White female living in the south central region of the United
States. Faith is an Evangelical Christian and attends a nondenominational church. She
described her experiences of living with her son, François’s mental distress.

Gia
Gia is an adult, White female living in the south central United States. Gia is an
Evangelical Christian who attends a nondenominational church. She described her
experiences living with her adult son, Gregoire’s mental distress.
Hannah
Hannah is an adult, White female living in a Midwestern town in the United
States. Hannah is an Evangelical Protestant Christian and described her experiences
living with her adult son, Hugo’s mental distress.
Table 1
Demographics
Participants Gender Church denomination State Relationshi
p to family
member
Mental health conditions
Adam male Pentecostal OH father anxiety disorders
Ben
male
Presbyterian
IL
sibling
schizoaffective disorder
Claudia female
Christian reformed
MI mother anxiety/depressive disorders
autism spectrum disorder
Deborah female Pentecostal MN sibling
bipolar disorders
schizophrenia
Elizabeth
female
Nondenominational
IL
wife
depressive disorders
Faith
female
Nondenominational
TX
mother
anxiety/depressive disorders
attentiondeficit/hyperactivity
disorder, autism spectrum
disorder, bipolar disorders,
OCD

Gia female Nondenominational TX mother anxiety/depressive disorders
bipolar disorders, PTSD
Hannah female Protestant MI mother
depression
schizoaffective
Data Collection
I collected data from one-on-one interviews with each of the eight participants.
All participants were interviewed just once because a second interview was deemed
unnecessary. Seven of the interviews took place via Zoom, and one was in person. The
in-person interview occurred in a secure area of the participant’s residence. The
interviews occurred on days and times convenient for all participants. I followed the
interview guide as noted and discussed in Chapter 3. Each interview was scheduled for 60
minutes, but the length of each interview varied depending on how much or little
participants were willing to share. I audio recorded each interview verbatim and did not
deviate from the data collection protocols detailed in Chapter 3.
The audio recordings were transcribed professionally into written form as soon as
I completed each interview. I removed filler words from the transcripts but refrained from
correcting the interviewees’ language or thought content. Then, I emailed each participant
a copy of their interview transcript to verify the appropriateness of the information they
shared and allow them to offer feedback (see Birt et al., 2016; Peoples, 2020). During this
process, only one participant revised the transcript by removing parts of the interview she
considered a digression or that contained information about other people with little
relevance to the mental distress experiences in her family. I secured all the data I
collected, including audio files and other documents I received from the participants,

such as the screening and demographic information. Names and identifying information
were removed to protect participants’ privacy. All these records are stored on a portable
storage device and kept secure in a locked safe. As specified in Chapter 3, I proceeded
with data analysis after assigning code names and removing any participant identifying
information.
Data Analysis
I used Giorgi’s (2009) descriptive phenomenological psychological data analysis
method to uncover themes contained in the interviews. The phenomenological attitude
was assumed by bracketing any preunderstanding of the phenomenon to listen to
participants’ accounts of their lived experiences. First, I read each participant’s entire
transcript while listening to the audio recording of the interviews to immerse myself in
the texts. My goal was to gain a general sense of the full description of each participant’s
experiences living with a family member with mental health challenges at home and in
their faith community. Through the process, I tried to capture the meaning participants
intended to convey through their description of the phenomenon as I brought into mind
the atmosphere of the interview and tuned into their experiences. No themes were
identified at this stage (see Giorgi, 1997, 2009).
After getting a sense of the full description of participants’ accounts, I continued
to assume the phenomenological reduction and read through the transcripts once more.
Then, I partitioned each narrative into smaller sections and identified meaning units in the

participant’s description from a psychological phenomenological perspective while
remaining mindful of the phenomenon under exploration, which was Evangelical
Christians’ daily experiences living with a family member with mental distress (see
Giorgi, 1997, 2009, 2012). In the third step, I played a more active role as a researcher,
using the process of free imagination variation to determine the essential structures of the
phenomenon (see Giorgi, 2009). The participants’ everyday expressions of their
experiences were transformed into themes that highlighted the psychological features of
their accounts (see Giorgi, 2009).
Using free imaginative variation once again during the fourth step, I transformed
the meaning units into consistent statements that described the essential structure of
participants’ experiences of living with a family member with mental distress in the
context of their faith community (see Giorgi, 2012). In this fifth and final step, I
compared situated, specific structures of each participant’s experiences to the others to
find where they merged and diverged. My purpose was to integrate the situated, specific
structures that revealed a general structure of the participants’ experiences living with a
family member confronting mental distress. I also highlighted the psychological
meanings in participants’ experiences (see Giorgi, 2009, 2012).
As I followed these steps immersing in the transcripts, clear themes about living
with a family member experiencing mental distress began to emerge from participants’
descriptions of their experiences. I identified main themes and subthemes that
encapsulate the general structure of participants’ experiences. After using Giorgi’s (2009,

2012) descriptive phenomenological method to analyze the data collected, seven themes
and 19 subthemes emerged to answer the research questions. Specifically, one theme
emerged from the data that supported the first subquestion regarding how participants
viewed mental distress. I also identified two themes to address the second subquestion
about participants’ perception of their faith community’s responses to living with a
family member experiencing mental distress. There was no discrepancy in the results of
participants’ statements about their experiences. All eight participants had lived or were
living with a family member experiencing mental distress, and they furnished details that
were consistent with their experiences. The results of the study aligned with the research
question and subquestions is provided along with data to substantiate each theme in the
Results section of this chapter.
Evidence of Trustworthiness
I ensured trustworthiness by establishing the study findings’ credibility,
transferability, dependability, and confirmability. From the study design to data
collection and the data analysis processes, I assumed phenomenological reduction by
bracketing previous knowledge about mental distress and living with another person’s
mental distress. Ultimately, participants in this study provided reliable and thick
descriptions of their experiences to establish the study’s trustworthiness.
Credibility
I established credibility by detailing the steps and procedures I used throughout
the study. I included excerpts of participants’ descriptions of their experiences so that

readers can evaluate the study findings and be confident that they represented
participants’ experiences. Member checking was employed twice, first by having
participants review the transcripts of their interviews and second by sharing the study
results with them to verify their accuracy.
Transferability
I did not modify the transferability strategies discussed in Chapter 3. While the
findings may only be transferable to Evangelical Christians living with a family member
experiencing mental distress as represented in the study’s sample, I have provided
information about the study setting and the data analysis method used. I have also
included thick descriptions of participants’ experiences so that any future researcher
interested in this study can authenticate the transferability of the findings.
Dependability
Future researchers and readers interested in verifying the dependability of the
study findings have access to the documentation I provided about the research process,
participant recruitment, data collection, data analysis, and thick descriptions of
participants’ experiences. In this study, I also benefited from the oversight of my
dissertation committee members who reviewed the research process and verified the
consistency of the steps taken to implement the study. The dependability strategies as
discussed in Chapter 3 were not altered.

Confirmability
I achieved confirmability in this study by establishing that the findings reflect
participants’ descriptions of their experiences. Verbatim participant quotes are provided
in the results to demonstrate that the explanation of the participants’ experiences of living
with a family member confronting mental distress emerged from their narratives. I also
engaged in bracketing to reduce researcher bias. The confirmability strategies stated in
Chapter 3 were not changed.
Results
In this descriptive phenomenological study, I explored and described Evangelical
Christians’ daily experiences living with a family member confronting mental distress.
One central research question guided the exploration of the phenomenon of interest: How
do Evangelical Christians describe their day-to-day life with a family member
experiencing mental distress? I also developed two subquestions to help me focus on
participants’ perceptions of mental distress and their views about the faith community’s
response to day-to-day life with a family member experiencing mental distress.
The seven core themes that emerged from the data analysis are:
1. An unpleasant and overwhelming experience.
2. A disease of suffering.
3. The costs of living with mental distress in the family.
4. Coping with the effects of mental distress in the family.
5. A supportive community.
6. An unwelcoming, unsafe, and unreliable faith community.

7. High expectations for leaders and congregants.
Theme 1, an unpleasant and overwhelming experience, included two subthemes
(a) confronting the unexpected and (b) defying despair and hopelessness. Theme 3, the
costs of living with mental distress in the family, had five subthemes: (a) sharing in the
suffering; (b) living with unpredictability and uncertainty; (c) physical and emotional
exhaustion; (d) closeness, broken relationships, and lost relationships; and (e) financial
perils. Theme 4, coping with the effects of living with mental distress in the family,
comprised five subthemes: (a) scrambling for answers and help, (b) united in adversity,
(c) finding comfort in God and spiritual practices, (d) finding purpose in suffering and
adjusting to life, and (e) managing mental distress stigma. Theme 6, an unwelcoming,
unsafe, and unreliable community, had three subthemes, (a) lack of structure for mental
health support services, (b) disappointment with faith community leaders, and (c)
disrupted fellowship with the faith community. Lastly, Theme 7, expectations for leaders
and congregants in the faith community, included four subthemes: (a) empathy and
acceptance versus blame and judgment, (b) mental health literacy and education versus
lack of mental health knowledge, (c) lasting versus short-term support, and (d) faith
leaders as mental health advocates.
I organized the themes into two overarching categories, which corresponded to
participants’ experiences living with mental distress, first within the family and secondly
in the faith community. I supported the themes with data from the interviews,
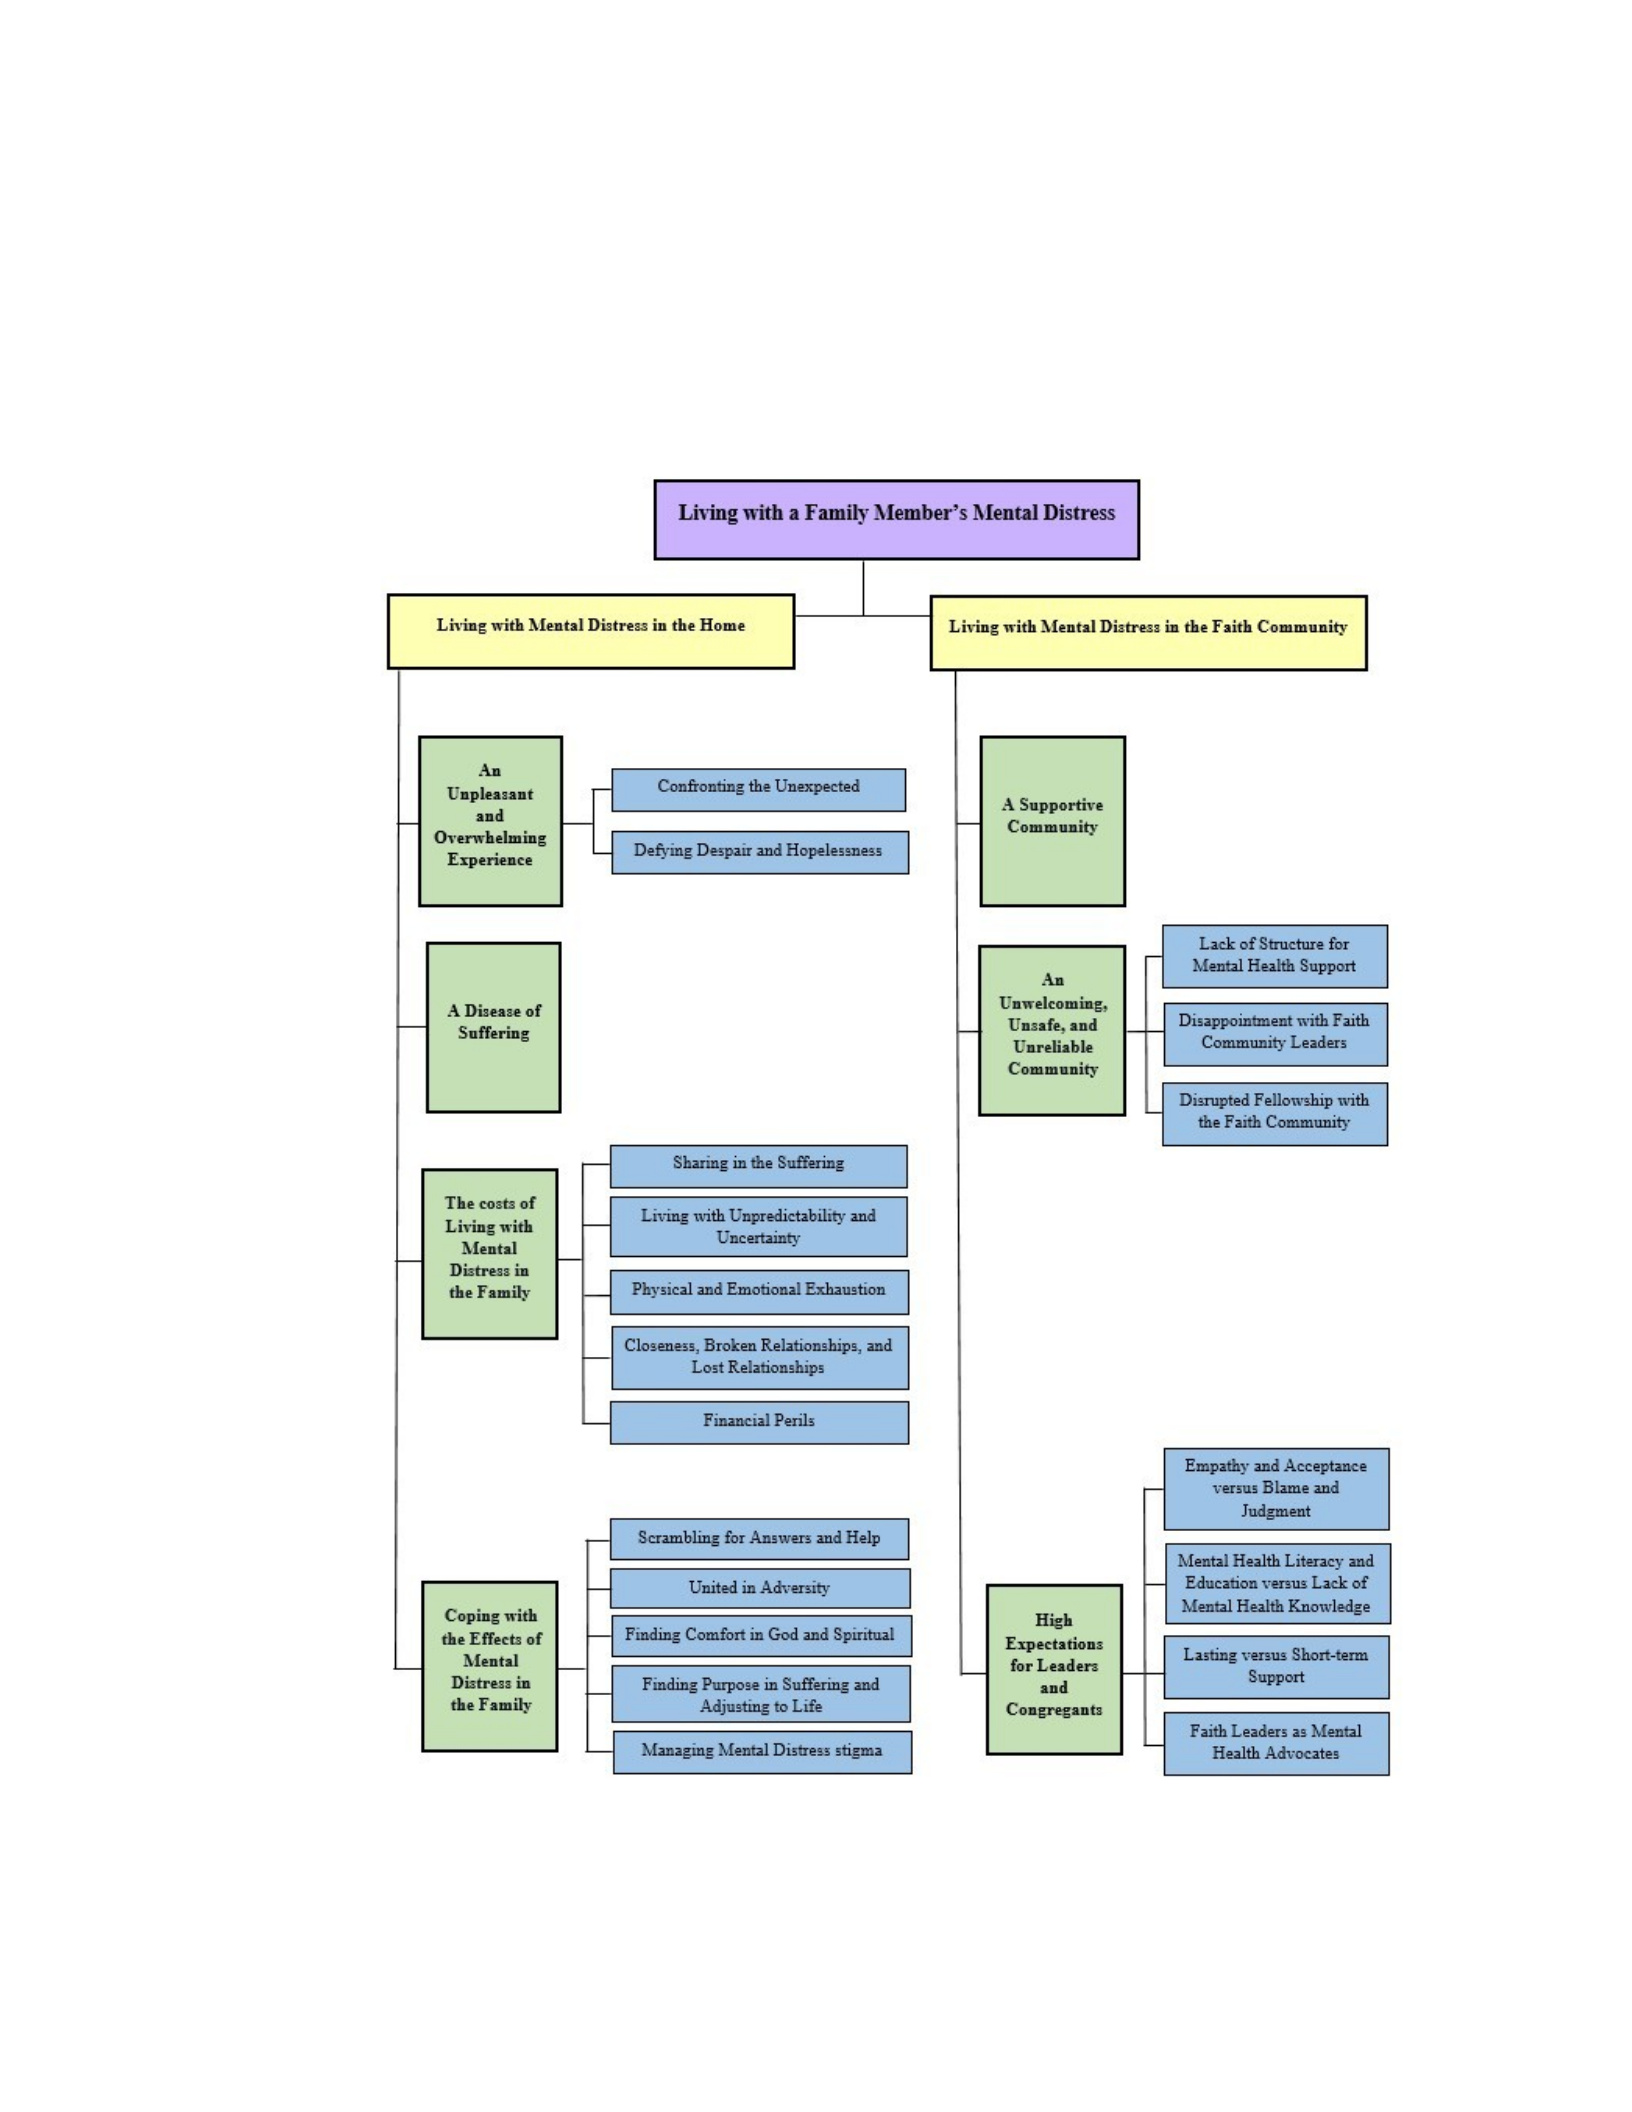
representing participants’ descriptions of their experiences of living with a family
member confronting mental distress.

Figure 1
Themes and Subthemes
Theme 1: An Unpleasant and Overwhelming Experience
The first theme that emerged from participants’ accounts of living with a family
member experiencing mental distress is how overwhelming and painful the experiences
were for members without adverse mental health conditions. All eight participants
reported experiencing a range of feelings such as frustration, sadness, worry, and fear at
various moments on their journey living with a son, daughter, sister, or spouse’s mental
distress. Participants described their shock, confusion, and worry at the unpleasant
changes in behaviors and the steady decline in functioning in the family member
experiencing mental distress.
Subtheme: Confronting the Unexpected (1a)
For participants, the family member’s mental distress caught them by surprise as a
novel but an overwhelming experience. They confronted the unexpected. Ben stated:
For us, it was a very learning experience. It was very discovering stage. What to
do with this new set of living conditions and symptoms that my sister has. We
were just scrambling to find out what exactly was wrong with her.
Similarly, Claudia said:
What started out as just, “I’m not good, and why did God even make me?” turned
into aggressive outbursts. Within a year we were having raging for hours. In fact,
we had him hospitalized for the first time when he was nine, after three-day rage,

literally. We had no idea what to do, so we decided to have him hospitalized at a
pediatric psychiatric hospital. … It was just such a shock for me when my son’s
issues started, because my first two kids, were so well behaved.
Gia made the unexpected and agonizing decision to hospitalize her son Grégoire
for his safety, as she was left with no recourse. As she noticed Grégoire’s aggressive
behaviors, Gia recounted that experience as follows:
At that point, I took him to a child psychiatrist. And she recommended, which is
really scary, only after about 20 minutes of meeting with him, “He needs to be
inpatient.” I’m like, “what?” I wasn’t expecting anything like that. My first
reaction was denial. Not denial that there was something wrong because
obviously there was, but denial that he had to be inpatient.
Gia described that decision as “extremely tough.” Faith and her son had multiple
visits with “psychiatrists and doctors and get all kinds of testing done just to figure out
what we were actually dealing with.”
Deborah also did not suspect mental distress in her sister until, as Deborah
recalled, Danielle “decided to just run off, and we couldn’t find her ... that was the
beginning where we realized something is wrong with her if she doesn’t want to stay in
touch with the family.” At that point, Deborah and the rest of the family knew that
Danielle was not functioning well.

When Hannah became aware of her son Hugo’s risky behaviors, she became
“quite concerned,” as she expressed. She “knew something was wrong.” Hannah recalled
that Hugo “just wasn’t himself.” Hannah and her husband had to rely on law enforcement
and act against Hugo’s will in his manic state to keep him safe or prevent him from
harming himself or other people.
Subtheme: Defying Despair and Hopelessness (1b)
Whether mental distress was anticipated or unexpected, those early days in the
family life were confusing, distressing, and terrifying for all the participants and their
family members. They prayed and hoped for relief as they sought answers to the mental
health concerns, needs, and challenges they were confronting. All eight participants felt
overcome and in despair fueled by their inability to alleviate family the member’s
suffering or control the effects of mental distress on the family. Adam expressed the
despair this way:
There’s that old saying that you’re only as happy as your saddest child, right?
When one of my kids is going through something, especially if it’s prolonged like
this, you always wonder why, or what can I have done, or and why isn’t God
healing her of this? I think that’s the struggles that I have.
Ben expressed the despair he experienced about his sister’s conditions, in his own
words:
What things can be done so that she can be protected and provided for? What
resources are there now that she could apply for? What things do I need to renew

so that she can continue to receive? What paperwork do I need to do? What legal
things are available options for her? For me? And how do I organize my schedule
and effort with my other sisters and my mom so we can take turns so I don’t kill
myself taking care of my sister? ... All these things are just draining and suck the
life out of you.
For Claudia, to deny that despair accompanies mental distress is to fail to
appreciate the totality of the experiences of people living with mental distress. She said:
I’ve also heard it said, “we can’t use the word suffering.” They did this in the
mental health community. I think they don’t want people to think it’s hopeless,
and most people do recover from a bout with depression; however, I feel that if
we leave out the reality of how much people suffer during these times of major
depression when everything is dark and hopeless, we are not helping them. Their
suffering is real, and by acknowledging it, we validate what they are
experiencing. If you paint it as something different, then you are minimizing the
suffering that people are going through because it is a disease of suffering.
Recalling the despair, Gia said of her experiences: “You’d wake up in the morning and
just don’t want to do this. I don’t want to do it again. I don’t want to do this.
But I’m a mother, so I had to get up and do it.” On
her part, Elizabeth said:
So, the typical pattern is he will then stop talking to me, and he doesn’t want to
engage ... I would love to see somebody together because those are the things to

work through on how we handle conflict. ... Now and then, there are these
moments where I go, ‘Okay, God is doing something.’ And God is gracious
enough to let me have a peek because sometimes, I just feel hopeless that things
are hard.
Hannah confronted that despair and its excruciating pain and described it as
follows:
Illness is a part of a fallen world, whether it’s cancer or mental illness. That
doesn’t change the character of God. But it is difficult at times to understand,
“what is the point of this person’s life?” is what I have to question. Maybe I
shouldn’t go there. But if this person is going to be in jail and in the hospital and
be homeless the rest of his life, what is the point of their life? ... What is the point
of all the suffering? Not only of him, but everybody around him?
Theme 2: A Disease of Suffering
I borrowed the title for this theme from Claudia, who referred to mental distress as
“a disease of suffering.” Claudia described the suffering she experienced in the following
terms:
Oh, it’s been horribly painful. Just horribly painful. We watched our son suffer
like that for 20 years from the time he was a little child. It’s awful. It’s
heartbreaking. It’s the worst. I couldn’t imagine that someone could suffer as
much as he has. I’ve had physical pain, and many people have pain for years, but

the mental anguish that someone with serious mental illness goes through, it’s just
absolutely horrible … if this brings up tears, it’s just recalling the suffering that I
saw him go through. That part was almost unbearable- watching him suffer.
The theme of suffering emerged from other participants’ descriptions of their
experiences. Faith indicated that mental distress in a family produces “suffering, pain,
and difficulty for everyone in the home.” Indeed, Adam suffered along with his daughter,
as he recalled, “and as she [the psychiatrist] was walking us through, we just had tears in
our eyes. It was just like our little baby, just going through all of that. Our heart just
really hurts for her.” Adam indicated further, “I don’t get angry at God. I don’t get bitter
at him. But it does leave a big question mark in my head as to why?”
Like Adam, Deborah suffered from Danielle’s mental distress, worrying about her
whereabouts, and pursuing any available opportunities to provide her with whatever help
they could afford. Lastly, Ben’s words highlighted the suffering inherent to living with
mental distress when he warned, “don’t get a mental disease ’cause if you got it, you’re
going to suffer.”
Theme 3: The Costs of Living With Mental Distress on Family Members
All eight participants described the long-term impact of living with mental
distress on family members. Mental distress in the family was as disruptive to the
functioning of family members as it was a risk to their well-being. All participants felt
and expressed the sacrifice they made, whether physically, emotionally, or financially to
accommodate their family member’s mental health challenges and needs.

Subtheme: Sharing in the Suffering (3a)
Mental distress in the family affects all its members, be they parents, siblings,
children, or a spouse. All participants experienced suffering and emotional pain in the
home at varying degrees due to mental distress. As Faith expressed: “mental distress
produced pain, suffering, and challenges in the home.” Adam explained the destabilizing
effect on him as “melancholy” or being on “a roller coaster.” For Ben, mental distress in
the family caused what he described as “a catastrophic change for all of us. And I don’t
think I’m the exception. I’m sure most, if not all, of the families who deal with their
family member’s mental illness goes through the same thing.” Claudia recalled the
emotional pain she endured watching her son suffer through his mental distress and
described it as “unbearable.”
Deborah spoke about the suffering they experienced together, saying:
We were just heavy-hearted and grieved and always wondering what we could do
to help her … in moments of prayer with my sister and my mother, we are
grieving over her. Yeah. It is heavy. It’s very heavy over us.”
There were days when Hannah’s suffering was so overwhelming. She asked in
her despair, “what is the point of all the suffering? Not only of him, but
everybody around him?”
Subtheme: Living With Unpredictability and Uncertainty (3b)
Mental distress dictated the pace of life for participants. The emotional well-being
of participants depended on the functioning of the individual with mental distress, whose

mental health needs also determined the course of daily life in the home. Participants
lived in fear or on alert of the next moment of crisis they could not always predict. Adam
expressed the tension this way:
When Adèle is struggling, it feels like there’s kind of a cloud. If she is in the
room or if she’s with us, it kind of brings everyone’s mood down a little bit. …
When
Adèle had an outburst, it’s not a great feeling because it just takes so much
emotional energy; however, after that outburst, it seems like things get better for a
while…when Adèle is healthy, which is most of the time, she’s a real delight.
Other participants described similar experiences. Deborah remembered that “there
was just a heaviness in the house because you just didn’t know what would set her off.”
Living with her sister’s mental distress was like “walking on eggshells.” Gia experienced
regular disruption in her day as she would have to stop whatever she was doing at a
moment notice and go to her son’s school to manage whatever crisis was happening that
day. She said: “pretty much every day the school would call me and tell me I needed to
pick him up. And I would go. I would leave my job”.
Ben shared his experience living life on constant alert as follows:
It takes a lot of people to take care of just one person. Even taking her to places, I
have to be mindful. I’m not just out there, walking a picnic with a friend of mine.
I have to be taking care of her so that she doesn’t get in trouble. When other
people look at her funny or when she makes a mistake of knocking something

down or she points at something that is socially inappropriate, I need to be on the
lookout so that she doesn’t hurt herself or other people.
Faith joined in saying: “We usually would travel anywhere in two different cars
so that when he reached his limit, somebody could take him home. And so, it started to
affect our daily living that way.” Faith added:
It takes a lot of waiting. It takes a lot of sitting. You know, a lot of appointments,
being flexed to change at a moment’s notice to what you need to do. If we got a
call, “Oh, mom, I’m on this side of the road. If somebody doesn’t come here and
get me right now, I’m driving off.’ Then we all drop everything, and we go.
Hannah recounted her experience with the uncertainty in her family:
When he is not well, he can get paranoid. Then he thinks his family is out to get
him ... so, we’re struggling with what to do when he gets out of jail. Do we go
down there and put him in the hospital again? Then, we start the whole process all
over again. That’s very difficult on our family, emotionally.
Subtheme: Physical and Emotional Exhaustion (3c)
Living with a family member experiencing mental distress was a stressful and
exhausting experience for the participants. Life was hectic and participants were busy and
sacrificially self-giving. The result of such commitment to the well-being of their family
member with mental distress is physical and emotional exhaustion. Deborah expressed
the stress and fatigue this way, “we had to give, give, and give to her. Afterwards, it’s
like feeling spent or overwhelmed with the amount of needs she has.” Claudia shared that

caring for her son’s mental health “took a huge toll on my physical and emotional
health.” Likewise, Faith confessed, “It’s affected me physically in ways, not just normal
parenthood does. It’s definitely a different level of stress.”
Gia and Ben’s descriptions highlighted not only the exhaustion that accompanied
living with a family member experiencing mental distress but also its severity. Ben
captured the fatigue he experienced as follows:
I have 24 hours a day. I cannot spend 24 hours taking care of her. I tried it, but I
almost killed myself. And I said this cannot go on. If I die, who’s going to take
care of her? I have to live!
Gia remembered those trying days saying:
Emotionally, it was exhausting. Just so exhausting. You’d wake up in the morning
and just don’t want to do this. I don’t want to do it again. I don’t want to do this. But I’m
a mother, so I had to get up and do it…I do remember one day pulling up to my mom’s
house with all three boys and walking in. I was just overwrought. And she told me,
“Leave them and go.” And I’m like, “No, I can do this. I can do this.” And she’s just like,
“No, you’re leaving the children here, and you are going. Just go.” Basically, she kicked
me out of the house and would not let me take my children because she could see that I
was emotionally distraught. I was exhausted. To be honest, I think she wasn’t sure the
kids were safe with me. Subtheme: Closeness, Broken Relationships, and Lost
Relationships (3d)
Participants often rallied to support each other and the family member with mental
health concerns; however, living with mental distress in the family has a real cost for

family interactions, affecting the nature and quality of those relationships. As participants
experienced in their family, there was emotional closeness but also loss of intimacy,
distant and broken relationships.
Ben described the nonreciprocal interactions with Barbara this way:
I don’t think she called or initiated any conversations. It was mainly us reaching
out to her…If and when she does visit home, we would bring her home or maybe
she did come by a bus, but it would be similar things at home…If the other sisters
were home, they would talk and stuff like that. But it was very different. It wasn’t
the same anymore ever since she came back… it was different in a negative way.
Deborah described the deterioration in the quality of her interactions with
Danielle saying:
Danielle could be so sweet and generous and fun. A great sense of humor. She’s
highly intelligent. She can be very responsible, and she was a good girl. She just
totally, just suddenly changed. ... Now and for about the past 10 years I would
say, she has been running away from us. She does not want to talk with us or have
anything to do with us.
Elizabeth portrayed the interactions in her marriage this way: “During his actual
depression and low times, I felt closer to him because God just did that.” Elizabeth added,
“in his depression if he’s really pushing, it’s hard to draw close ... the spiraling of pushing
me away and me staying away just makes the conflict or the tension in our marriage
skyrocket.”

Interactions with adult children living with mental distress adds a layer of
complexity to existing trying interactions. Claudia said the following about their
motherson interactions:
Christophe and I had a good relationship when he wasn’t upset. We would talk…
and I did things with him all the time. He was obsessed with Star Wars. So,
I’d watch Star Wars movies with him. He loved Legos. I’d build Legos with
him…But if something would make him blow up then he would get aggressive,
and I had to listen to him screaming and raging around me.
Describing the quality of the mother-son relationship through different seasons of
life as well as how mental distress affects their relationship, Hannah said the following
about Hugo:
When Hugo is functioning well, we have a great relationship. He knows his
family loves him…when he is not well, he can get paranoid. Then he thinks his
family is out to get him and people are out to get him. It’s difficult because we
want to do the right thing. But then, he doesn’t like it when we put him in the
hospital. Then he gets angry at us. That’s difficult.
Subtheme: Financial Perils (3e)
Participants went to great lengths to secure mental health services for their family
members or keep them safe and protect them from harm. The financial strain of caring for
mental distress in the family was often taxing as they had to spend sacrificially. Ben said,
“my life has changed in terms of my finances. I spent a lot of money taking care of my

sister.”
Like Ben, Claudia said:
There was also a big financial burden on our family. When Christophe was
younger and getting treatments or being hospitalized there was no ‘mental health
parity,’ so we had huge medical bills several times. We had to go into our
retirement fund to pay for his hospitalizations.
Hannah commented in agreement with other participants saying: “I had to quit my
job. Many women especially are staying home to care for their adult son or daughter with
mental illness which has, of course, a financial effect, too.”
Moreover, the lack of financial resources was often an obstacle to receiving
adequate care or professional support, which added to the frustration and stress in the
family. As Elizabeth remarked when her friend encouraged her to seek counseling, her
response was: “we can’t pay for it.” Ben also recalled his frustration about the
unaffordability of mental health services as he sought professional support. He said: “I
expressed my concerns for my sister, and they had evaluations, and plan of treatment and
options and stuff like that, but I couldn’t afford it. It was very expensive. … I was not
only discouraged but very angry.”
Theme 4: Coping With the Effects of Living With Mental Distress in the Family
The fourth theme that originated from the participants’ descriptions is coping.
Living with a family member experiencing mental distress in the family was an
emotionally, financially, and logistically taxing experience for every participant in the

study. Despite the despair and challenges the participants confronted, they found ways to
adjust and live as productively as possible.
Subtheme: Scrambling for Answers and Help (4a)
All eight participants demonstrated a commitment to finding solutions to the
mental health needs in the family while also maintaining functioning under demanding
circumstances. They sought support from different sources including, friends, mental
health professionals, mental health organizations, and faith leaders. Ben said, “we worked
through different agencies, doctors, psychiatrists, counselors, in and out of the church,
family connections and whatever. We were just scrambling to just figure out.” Faith
added, “As far as our support, I got involved with NAMI which is National Association
of Mental Illness about three years ago, and that was probably the biggest support for
me.”
Claudia also sought help from health professionals. She recounted:
When Christophe was 12 years old, he started having almost constant suicide
ideation. My fear of him dying by suicide was real, and we knew that something
had to be done. I found a private psychiatric hospital in a neighboring state, that
someone highly recommended for anxiety. We took him there and spend 2
months getting treatment.
Subtheme: United in Adversity (4b)
In families with mental distress, members found comfort in one another in their
shared suffering even as they rallied together to meet challenges. Adam said:

My wife and I, we always have weekly date nights. So, we’ll go out and get a bite
to eat or something. We talk about ourselves, but we also talk about our kids:
‘what are we doing for Adèle?’ It was more a lot of conversations. Sometimes
feeling a little bit hopeless.
Ben and other members of his family “visited her [Barbara] pretty much every
week” at her school to make sure that she was well. On her part, Deborah recounted her
family’s commitment to her sister as follows: “that [conversation about mental distress]
didn’t come until much later when we realized that she was not functioning as a young
adult. She was not functioning. So, we decided that she could use some help. Of course,
we tried to get her help.” Lastly, Gia spoke of counting on her mother’s support, saying:
“It was difficult because I was a single mom at that point with three kids that I was trying
to raise. My mom was a godsend to me. She just took on the kids. She was just amazing.”
Subtheme: Finding Comfort in God and Spiritual Practices (4c)
All participants turned to their faith in God and spiritual practices to find comfort
and support. Participants turned to God for answers. They also credited God for the
strength to overcome daily stress and suffering. God was the anchor and partner. Adam
said:
For me, it’s like two-part harmony, right? I do my thing as a parent, or we do our
thing as parents, and then God does his thing as God … I feel like God’s with us.
He’s guiding us. He’s giving us direction and that’s been a lifeline to us. We lean
on him big time.

Like Adam, Elizabeth found support and strength in her faith. She said: “I’m
thankful for my faith that I can lean on the Lord and know I can pray and ask Him to give
me the words.” Similarly, Hannah found comfort in reading the Bible. She said: I think
you can look to stories in the Bible of people who suffered like Job, for example. He had
a lot of friends, too, that came around that didn’t get it. I find that helpful to read those
stories.
For Deborah and her family, weekly prayer became a regular practice that sustains
them. She stated: “We still pray for her. About twice a week we pray together. My
mother, older sister, and I do pray for her.” For Faith, living with mental distress in the
family requires sensitivity to the presence and guiding of God’s Spirit. She said:
“Honestly, for me, it’s about staying in step with the Holy Spirit leading me and guiding
me every day.”
On her part, Claudia said:
Having been a Christian for many years, and having the privilege of learning the
scriptures, and growing spiritually when I was a young adult, prepared me to be
able to trust in God when things were hard. My experiences have shown me how
important it is to grow spiritually before you have the big difficult things in your
life that everyone experiences eventually. This helped me to not question why but
to be able to trust in the Lord who loves me. I had to be strong because I had to be
my son’s advocate. My trials didn’t take me away from God. I can say that my
son’s mental illness made me rely on and trust in God even more than when life

was carefree. Our God is trustworthy, loving, and faithful.
Subtheme: Finding Purpose in Suffering and Adjusting to Life (4d)
Participants appeared to have reconciled their experiences when living with a
family member confronting mental distress to find acceptance and meaning in their
experiences through the mediating role of their religious beliefs and practices. Reflecting
on how he made sense of his sister’s mental distress, Ben said:
Well, first of all, I’m reminded of it frequently that we live in a fallen world. This
is a broken system. Things are broken and things are breaking even as we speak. I
think that’s just a matter of fact as a Christian. But saying that, we have the
responsibility and opportunity to use it as a platform to taste the Kingdom of God
here and now and do the things that we can to show God’s love to this world.
Claudia shared her unwavering trust in God’s purpose. She credited her
relationship with God as instrumental in adjusting to the challenges of living with her
son’s mental health challenges. She said:
I don’t think my faith changed the way I look at mental illness, except I hope it
has made me more compassionate towards people who experience it. I think faith
in a God who loves you, helps you to be able to receive help from your God.
Without my faith, I don’t know how I would have been able to get through the
hardest years.
Claudia has also found inspiration in her experience, adding:

My son is one of the strongest people I’ve ever known. He hasn’t accomplished
much as an adult in the eyes of most people, but he hasn’t given up and keeps on
trying after 22 years starting as an 8-year-old. He is my hero.
Other participants experienced growth in empathy and humility. Hannah said:
This [living with her son’s mental health conditions] has opened my eyes to
others that are, of course, suffering. So, I’m more aware of other people and their
issues that they’re dealing with. I’m not so quick to judge anymore other people
and their problems. So, that’s a good thing. It’s humbling. You have to ask for
help.
Faith has also learned to be patient, accept, and adjust her expectations through
difficult times. Faith explains the meaning-making process saying: “He [God] doesn’t say
he’ll take all suffering away, but He does give us a way of escape as we go to Him.”
Faith has also grown appreciative of her experiences and her children. She said:
I think it’s deepened my faith and my walk because of what we’ve experienced…
God’s called me to something within my own family, which is maybe what I
didn’t expect, maybe what I didn’t necessarily sign up for. But at the same time, I
wouldn’t change it for the world.” Then she added, “even my oldest she’s almost
22. She’s married now and she works with deaf and special needs kids ... same
with my 18-year-old son. He works with special needs kids at our church. And he
volunteers to be buddies with them, you know? I think that’s because he saw the
struggles of his own brother, and he couldn’t always understand it or be there for
his own brother, but he wanted to be there for someone who wanted him to.

Gia described a change in perspective that gave her meaning. She recounted that
moment, sharing it with her mother this way:
I pulled my car over to the side in the parking lot, totally turned it off, and I just
said, “Oh, my God.” I said, “God, I understand. I know now why we went
through this.” I said, “We went through this so that you could guide me to help
other people.” From that day forward, I’m crying here. Sorry. From that day
forward, I really have just a whole different sense about it. I became a lot more
passionate about teaching people about it.
The change in perspective allowed Gia to accept her son’s mental distress, which
produced spiritual growth and peace in her. Gia said:
It did bring a lot more peace to my life ... I really think that helped me take one of
my first big steps in my faith. So, I’ve done a heck of a lot of praying since.
While my son has been arrested a number of times due to his outbursts from his
illness
or due to self-medication; while all of that, I’ve still been able to remain peaceful
about it and just realize that worrying about it is not going to change how
anything is laid out, and I had to hand it over. And I think that helped me to learn
how to hand things over.

Subtheme: Managing Mental Distress Stigma (4e)
Learning to endure or address mental distress stigma inside and outside the family
was vital to living well with mental distress. Some participants worked hard to dispel
stigmatizing beliefs surrounding mental distress in their families and faith communities.
Claudia said:
You often miss holidays with family. You can’t go to Christmas because your
child is too anxious to go to Christmas with the extended family. You can be
accused of giving in or babying them when you can’t go … I think it was one of
the last times Christophe was even part of our family Christmas with my
husband’s family, he started getting anxious … he lost it in front of grandma and
grandpa and his aunts and niece and cousins for the first time. And afterwards, I
get emails from family: “well, mom and dad shouldn’t have to put up with that,”
and they didn’t want their kids seeing that.
Hannah also confronted mental distress stigma in her family. She recalled: We
just had an issue with my sister-in-law who decided to use my son as an object
lesson for her children what not to do, not to go in jail. Well, we had to have a
discussion with her that it’s not that he is purposely being a bad person to get
arrested. It’s part of his illness. So, we have to do a lot of education of family
members because they don’t understand mental illness.
Deborah was concerned about mental distress in her faith community. She said:

“Well, we don’t share [Danielle’s mental health challenges] with a whole lot of people.
We don’t tell people. In my fellowship group right now, I don’t share it with them … the
most hurtful thing is that we can’t share it with them.” Likewise, Ben acknowledged that
“there’s stigmatism against or towards mental illness. And so, we don’t openly talk about
mental illness at church. It’s very individual and in isolation.”
Faith is also aware of mental distress stigma in her faith community and is
determined to combat it. She said:
I don’t think the church is as familiar with all the different stages of mental
illness. Some people - it’s just a stereotype or stigma…our goal as a group is to
liaison with other churches to unite - for people to understand, and to break down
stigmas and walls.
Theme 5: A Supportive Community
Half of the participants (n = 4) expressed their appreciation for the spiritual,
social, and financial support they found within their respective faith communities. Adam
praised the efforts of his faith leaders to address mental distress in the church, saying:
And they’ve actually talked publicly from the pulpit about it, which I thought was
really beautiful, both from a standpoint of therapy and medication, and God. So, a
real holistic approach from the pulpit, which is good. They’ve also had counseling
available; they did have a counselor on staff for a while … so, I think they’ve
done well, providing both counseling services and for the rest of the church,
speaking to it in a healthy way. That’s been good.

Likewise, Claudia was pleased by the faith community members’ expression of
love and care to her family. Claudia said:
Before Christophe went to the hospital for four months in another state, we did
reach out to our church family. Before he left, they had a prayer meeting for us on
a Sunday afternoon. There was about 50 people that showed up. People went
around, and everyone prayed for us and for Christophe. I was sobbing the whole
time. We still go to the same church, and for years people have asked me about
him even now. They also helped us some financially during his hospitalization.
Elizabeth and Hannah also reflected on their positive experiences within their
faith community. Elizabeth acknowledged it, asserting: “I couldn’t have done it without
them. They were the ones that held my hand, and we walked through it ... I felt very
supported, and they continually reached out.” Similarly, Hannah found support in her
church and enjoyed the opportunity to speak about how mental distress affected her
family. She said:
We have a small group that we just joined, and the last time we met, we talked
about struggles with mental illness. It is nice to be in a group where people feel
free to share, whether it’s themselves or a family member that’s struggling.
Theme 6: An Unwelcoming, Unsafe, and Unreliable Community
In faith communities where families living with mental distress found support,
participants described their disappointment with the faith leaders’ attitudes and lack of
interest, decision-making processes, inaccessible resources, and lack of understanding

about mental distress present in the faith community. Instead of empathy, participants
encountered judgment and stigma fueled by unfamiliarity with mental distress. Adam
wanted his daughter and other people living with mental distress to be welcome and
integrated into the life of congregation. He was profoundly disappointed that his daughter
found support and acceptance in secular institutions but not in his faith community. He
wondered: “if the public schools can figure that out, why can’t the church have a little
more empathy? Right?”
Ben and his family members were aware of the mental distress stigma in the
church, preventing them from reaching out for support. He said: “there’s stigmatism
against or towards mental illness. And so, we don’t openly talk about mental illness at
church. It’s very individual and in isolation.” Like Ben, Deborah did not feel safe sharing
her sister’s mental distress experiences with fellow congregants. It was a private matter to
avoid mental distress stigma. Deborah recounted:
I only tell my very close friends. We don’t tell the whole church about it.
Actually, the small group that my husband and I are involved in -- we don’t share
her in detail because we don’t want it to reflect badly on our family either. So, it’s
a little bit of, we don’t think they can help, and we don’t want it to become gossip
and rumors.
Faith and Hannah also experienced mental distress stigma in their respective faith
communities and attributed it to congregants not being well-informed about mental
distress. Faith suggested: “I don’t think the church is as familiar with all the different

stages of mental illness. It’s just a stereotype or stigma.” On her part, Hannah reported:
They don’t understand. Some people think it is demons. That’s not helpful either if they
think it’s just a spiritual problem … whether it is, they don’t have enough faith, they
don’t pray enough, there is that guilt trip and that judgment, unfortunately, in the faith
community. That is a sad thing. They want to blame the victim. They want to blame the
family for this … yeah, unfortunately, we have.
Subtheme: Lack of Structure for Mental Health Support Services (6a)
Almost every participant deplored the unwelcoming environment and inadequate
structures in their faith communities to offer support services that address the needs of
individuals and families living with mental distress. Either their faith community was
illequipped to provide mental health resources and services, or church programming
overlooked the mental health and spiritual needs of families living with mental distress.
From the participants’ perspectives, the lack of mental health support services
represented a missed opportunity, suggesting that congregants and faith leaders were not
listening to the concerns of families living with mental distress. Adam stated:
It’s building more empathy because I think that’s probably what’s missing- that
empathic ability to say, wow, you go through all of that on Sunday, or a
Wednesday or whenever we’re doing programming. Wow, that really helps us. So
then maybe get into a dialogue with us: what could we do to maybe make it easier
… I think it’s competing priorities, and I just feel like our priority is her health
and wholeness.

Hannah echoed the same sentiment saying:
I think it would be helpful if the church did have a better understanding of how
the family is affected by it and how they can support the family in a way that is
nonjudgmental. I guess that’s what the church is often accused of, right? Being
judgmental. We’ve experienced it firsthand.
She added, “it is unfortunate that you have to go outside the church to get that
help.
Ben expressed his disappointment with the lack of support for families and
individuals living with mental distress as follows:
But when you look at the church announcements or bulletin boards or whatever,
there wasn’t a really well-developed way of support, listings, and volunteering. It
was more of a personal basis, right? So, you had to go to see the pastor, and what
he knows or what she knows, however it is setup, and then they would refer you
to some places. But it wasn’t available out there for people to find out and just
learn about it … I think a lot of churches lack the resources to provide a sufficient
amount of education and support for mental illness.
Claudia explained the lack of interest in faith communities to offer mental health
programming saying:
A couple of years ago they held a Mental Health Learning Community. My
church was part of this, and I participated. It ended up being about five churches
which is sad because they contacted every single one of the 300 or so churches in

the denomination in our area. The small number of churches willing to participate
shows that people don’t see it as a need. … Many churches do not understand
mental illness, and that’s the whole core of the problem.
Subtheme: Disappointment With Faith Community Leaders (6b)
Overwhelmingly, participants voiced their disappointment with their respective
faith community leaders. The participants’ accounts depicted faith leaders who seemed to
show little interest in families and individuals living with mental distress by their
conspicuous inaction. The faith leaders seemed to be preoccupied more with church
functioning and prioritize the spiritual needs of the congregants at the expense of their
mental health needs.
Adam believed that the faith leaders underestimated congregants’ needs when
their focus was to encourage church attendance while overlooking the concerns of
individuals and families living with mental distress. He said the faith leaders made
“unilateral decisions from up here that I think are very obtuse and can really have a ripple
effect.” Adam added, “I think it’s competing priorities, and I just feel like our priority is
her health and wholeness.” Hannah lamented the lack of resources from faith leaders,
stating: “It is unfortunate that you have to go outside the church to get that help.” Ben
expressed his disappointment with faith leaders, stating:
When there is no budget allocated for mental illness, 9 out of 10 times, nothing’s
going to happen. ... We should care for the needy people, including the mental
illness people. But when we come to setting the budget, that doesn’t get included

as much … you can’t say you care about the mental illness if you don’t put any
money in it.
Deborah’s lack of trust in faith leaders appeared to be their failure to teach about
mental distress and create an environment of trust and compassion that supports
individuals and families living with mental distress. Deborah shared:
If they spoke more openly about mental illness … or if we were educated as a
church about different mental illnesses, what to look out for; and if there was
some lay counseling just to open the door; and more prayer for healing and people
who are trained in it … then we could trust them.
Deborah added, “I think a lot of churches do a lot of Bible studies, but they don’t
explore this kind of issue. They do overseas missions, or they do women’s Bible
studies, but they don’t really look into that.”
Elizabeth was dissatisfied with the lack of interest from her faith leader. Elizabeth
said:
When we told him [the pastor], he prayed for us when we shared the situation. We
had an event that we held for an outreach. And when I showed up without
Édouard, I said, “He’s having a really hard day.” But our pastor never, at least to
my knowledge, reached out.”
Faith shared a similar sentiment saying the following about his son’s mental
distress experiences: “His youth pastor and church and our pastor know that there’s been

struggles. But to say that we really had support in that within our church or in our
community, not necessarily.”
On her part, Gia’s endeavors to persuade her faith leaders to support her initiatives
to offer mental health services failed. She reported:
We wanted to get some courses out here in our area because we didn’t have
anything. I asked my church about space, and they kind of hemmed and hawed
and didn’t really come forward with an answer for a while. Then when they did,
“it was there wasn’t room.”
Gia contacted the church leadership again, for a second time:
I have asked about perhaps trying to head up a mental health ministry at the
church. And, again, hemmed and hawed. Didn’t really get a real straight answer
… so, in some ways I was shocked because I would’ve thought they would’ve
fully embraced this.
Subtheme: Disrupted Fellowship With the Faith Community (6c)
Participants’ responses to the mental distress stigma, the lack of empathy, and the
lack of adequate supporting services in their faith communities were diverse. They ranged
from being disappointed in the faith community, hurting in silence, feeling excluded from
church programming, and not fully belonging in the faith community’s life. Mental
distress disrupted participants’ full involvement in the faith community’s life.
Adam deplored church programming that did not facilitate his daughter and the
family’s full participation in the faith community. He said:

Yes, now there is a structure. I think if it was quieter, and Adèle had structure and
she knew what to expect … and maybe make some accommodations for kids that
don’t like loud music and flashing lights. I think it’s fun. But I think that there’s
some kids that that can scare them. So, I think some of the feedback that we were
giving them somewhat fell on deaf ears.
Although Deborah desired full participation in the life of her faith community.
Deborah kept an essential aspect of her life private from fellow congregants to avoid
judgment or rejection. Deborah said, “In my fellowship group right now, I don’t share it
with them. … The most hurtful thing is that we can’t share it with them.”
Many participants sought help outside of the faith community. Ben said:
I didn’t get much luck with Christian counseling or churches. I did end up having
somewhat of a support from one psychiatrist who was a family friend ... I knew
another psychiatrist from personal relationships. She was helpful when she was
down there. But other than personal relationships in ministry, I didn’t get too
much help. Well, I shouldn’t say I didn’t get too much help. There wasn’t a
system that we could really benefit from, though.
Faith also sought and benefited from outside support. She stated:
But as far as our support, I got involved with NAMI, which is the National
Association of Mental Illness, about 3 years ago, and that was probably the
biggest support for me. ... That was definitely probably the biggest, both

educating and supportive resource that we had, and we wished we had had it 5
years before that.
Some participants were willing to leave their faith community for a more
welcoming one. For instance, Adam mentioned:
The other thing is we’re working through faith with her, and we would be willing,
even though we’ve got quite a few family members attend this church, we would
be even open to going to another faith community if it meant her being provided
what she needs. And maybe even just where does she feel that she’s most
comfortable and safe? Where does she feel the most connection?
While Adam and his family have not left his faith community, Hannah did. She
recounted:
We left the church. Went to a different church. Fortunately, it was easy to do
because I got a job at the new church, and we had to become members. So, it was
convenient to leave. We were looking to leave anyway.
Theme 7: High Expectations for Leaders and Congregants
Participants’ accounts of their experiences living with a family member
confronting mental distress painted the faith community as the missing piece in their
endeavors to live productively. Adam said:
For me, it’s like two-part harmony, right? I do my thing as a parent, or we do our
thing as parents, and then God does his thing as God, and together, hopefully with
the faith community, that’s a really good kind of three-legged stool. I would say

the faith community, I’m not saying they’ve let us down, but that’s probably been
more of a struggle than the other parts of it.
Faith echoed the sentiment expressed in Adam’s accounts, saying that the faith
community has “probably been one of our biggest, I don’t want to say challenges, but a
harder area.” In all, participants expected the faith community to be a safe and
accommodating place for families and individuals with mental distress. They expected
the faith leaders and fellow congregants to understand and support their efforts to
function despite the daily challenges.
Subtheme: Empathy and Acceptance Versus Blame and Judgment (7a)
Adam wanted to see members in the faith community grow in their compassion
towards families and individuals living with mental distress in the faith community. He
said:
A great exercise would be to have an interview. Or I don’t know if there’s
anything like this out there to walk through what a Sunday would be like, or a
Wednesday or whatever day would be like, for a family like ours to come to your
thing. What would that be? What’s that like for her, and what’s that like for us as
parents? And so, it’s building more empathy because I think that’s probably
what’s missing- that empathic ability to say, wow, you go through all of that on
Sunday, or a Wednesday or whenever we’re doing programming. Wow, that
really helps us.

Gia also exhorted fellow congregants, saying: “If you see someone who is
obviously in mental distress, don’t put yourself in any danger, but reach out to them
however you can, just to show them that they’re a person.” Like Gia, Claudia urged
empathy, suggesting the following: “Don’t judge these families, or individuals that are
living with mental illness. They are probably trying harder than you know. Just show
them loving concern and support them in whatever way you can.” Hannah concluded, “I
think it would be helpful if the church did have a better understanding of how the family
is affected by it and how they can support the family in a way that is nonjudgmental.”
Lastly, when asked what members in her faith community could learn from her
experiences living with mental distress in her family, Faith said:
If anything, one of the things that both the Lord’s taught me and then in my
research and then just with NAMI and the different things I’ve learned, is learning
empathy and compassion in a new way. Not only how to express it towards my
son but maybe towards other people who are in those experiences. Just the
acceptance that you’re still just a beautiful creation and Christ has made you this
way, and it’s not bad, and it’s not wrong.
Subtheme: Mental Health Literacy and Education Versus Lack of Mental Health
Knowledge (7b)
Participants described the adverse impact of mental health illiteracy in their faith
communities on their experiences of mental distress in the family; consequently, they
advocated for mental health education and training to address mental distress stigma in

the faith community. Hannah shared her perspective, saying: “I think that we need to do a
lot of education in the church because I think some people assume that somehow the
victim is to blame for this illness…I think that a lot of it stems from ignorance.” Claudia
also addressed the issue of mental health illiteracy as follows:
Many churches do not understand mental illness, and that’s the whole core of the
problem… I think we need to start with education. The church will not react to
help people with mental health struggles if they don’t even understand what it is.
If they don’t see that it’s causing as much suffering as physical ailments, they are
not going to step up to the plate and help people. So that’s where I think we need
to start. Some people will say, “Well, the church isn’t the place to educate.” Well,
you don’t have to do it during your church service. You can do it during the week
on Wednesday night or whenever. But I think that has to start there.
Like Claudia, Adam believed mental health education in the faith community was
an appropriate response to the stigmatization of individuals and families living with
mental distress. He said:
I don’t think we felt a lot of judgment. I think it’s been probably a little bit
occasionally just ignorance. So, I think better education would help with better
understanding. I think anytime you can educate people better in a healthy way, the
empathy rises, and the ignorance decreases. I think that’s a space for health and
healing for our faith community.

Subtheme: Lasting Versus Short-term Support (7c)
Another challenge participants described facing was inadequate mental health
support from faith leaders and fellow congregants. Whether spiritual, financial,
emotional, or physical support, participants believed receiving long-term support would
make a positive difference in their experiences of mental distress in the family. Deborah
attributed the lack of support to the misconception about mental distress, saying: “I think
sometimes there is lack of compassion [from faith community], … lack of compassion
because people are quick to judge. They don’t understand that it could be a mental
chemical imbalance sometimes in that person.”
Faith explained the mental health support she desired but did not receive from her
faith community as being inadequate. She stated:
I think what ends up happening with mental illness is it’s a different kind of
sickness. But families need that same type of care at times from within the church
body that people don’t understand. They need it just as much because it’s a
different sickness, but it affects not just one person, but it tends to affect the
whole family.
Hannah said the following about the inadequate support in the faith community:
They [faith community members] were great at first, but then they dropped off.
… It would be great if the support continued beyond the crisis. It seems that when
you have a crisis, people might show up and pray for you. But after the crisis is
done, then there is no more support.

Claudia believed the church could provide physical and tangible support for
families living with mental distress because of its long-lasting effects. She said: I think
people who have younger children with mental illness would be helped by the church
providing some respite. … Many families that have children with mental illness deal with
it for many years. Families often have support at first from their church, but that tends to
slack off after a while. So, churches could help families by not forgetting them even if
their child continues to be ill…Having some offer to stay with their child so they can go
to worship occasionally together would be very nice.
Subtheme: Faith Leaders as Mental Health Advocates (7d)
All participants viewed the faith leaders as influential actors in congregants’
experiences of mental distress in faith communities. Therefore, participants expected
faith leaders to talk about mental distress regularly, engage individuals and families living
with mental distress, and advocate for their mental health needs in the faith communities.
Participants wanted faith community leaders to foster an environment that supported
mental health literacy.
Hannah believed it was the faith leaders’ duty to provide mental health education
in the church. She said, “I think that we need to do a lot of education in the church.”
Similarly, Deborah underscored the responsibilities of leaders in the faith community to
educate about mental distress and create a community of caring and compassionate
congregants, saying: “So maybe just more education, educate church people to be aware

of it [mental illness] and how to handle it, how to help one another; not gossip, and just
have compassion.”
On her part, Faith believed leaders in the community could create and make
accessible a structure in the church to support the mental health needs of congregants.
Faith recalled:
And so, when I look back when we weren’t sleeping, and he wasn’t sleeping for 4
months, would having meals or people taking my little kids so I could sleep been
helpful? Absolutely. It would’ve been a world changer. But you don’t know who
to reach out to or who to ask because it’s like they don’t really know what you’re
dealing with.
Ben offered faith leaders the following suggestion:
Rather than being reactive to a problem, the church could be proactive in figuring
out, in the name of this Gospel, how can we be the salt and the light of this world?
Do we just sit around and twiddle our thumbs until somebody comes knocking on
the door? Or could we search and look around parish members, their relatives, or
geographic neighbors and see where they are? Are there some families who are
experiencing mental illness? How can we help them? By asking those kinds of
questions in the first place is a huge thing I think the church can learn.
Adam believed faith leaders’ commitment to engage families and individuals
could make a difference. He suggested leaders could “maybe get into a dialogue with us:
what could we do to maybe make it easier?” Like Adam, Gia believed it was the faith

leaders’ responsibility to make mental health resources accessible to congregants if only
they listened to congregants. She said:
I would’ve liked them to maybe, number one, to welcome us having our NAMI
course there just to start it. I would have liked them to invite us as a NAMI out to
speak to the elders and to speak to the pastors. If they talked to us about support
groups or about a mental health ministry and didn’t like what they had to hear
from us, that would’ve been one thing. But they didn’t really open the door to it.
So, I would’ve liked a little more willingness to listen to learn.
Discrepant Data
Participants in this qualitative study described their experiences of living with
mental distress in their families. I noted the similarities in their narratives and highlighted
them in the themes I described in this chapter. Some participants, however, reported
noteworthy features of their mental distress experiences within the family despite the
commonality. Findings from participants’ descriptions showed that they were united in
their support of the family member with mental distress; however, two participants shared
occasional tense interactions amongst some family members due to mental distress in the
family. First, one participant mentioned marital discord in her family of origin as one
parent blamed the other for their daughter’s mental health challenges, attributing mental
distress to parenting style. Another participant reported misunderstanding from their adult
children who believed their parents were indulging the sibling with the mental distress,
resulting in occasional conflictual interactions.

In another instance, a participant’s accounts painted a picture of someone who has
become cynical about his experience of living with mental distress in his family of origin.
As I highlighted in the themes, other participants expressed their disappointment about
the lack of resources in their faith communities; however, this participant’s expressed
cynicism stood out and did not emerge as central in other participants’ experiences.
Summary
This chapter detailed my process and strategies for conducting the research. I
described the setting of the study, including information about the participants, the data
collection process, and data analysis. I reviewed the findings’ credibility, transferability,
dependability, and confirmability, furnishing data to support the study’s trustworthiness. I
proposed seven essential themes that emerged from the eight participants who shared
their experiences living with a family member facing mental health challenges.
Altogether, participants’ candid and thick descriptions gave readers perspectives on
mental distress as a disease of suffering producing damaging effects on the family. The
findings highlighted the role of participants’ faith and religious practices in adjusting to
the despair and demands of living with mental distress. The results revealed the stigma
and inadequate mental health resources available to participants in their faith
communities.
In Chapter 5, I will interpret the findings of the study in the context of the extant
literature on Evangelical Christians’ mental distress experiences. Then, I will make
recommendations for further research after describing the limitations of the study. Lastly,

I will explain the potential for the study findings to foster social change.
Chapter 5: Discussion, Conclusions, and Recommendations The
purpose of this descriptive phenomenological study was to explore and describe
Evangelical Christians’ everyday life with a family member who experienced mental
distress. In-depth interviewing was used to collect data, which offered the research
participants the space to liberally tell their stories through the lens of their religious
beliefs and membership in a faith community. I explored participants’ views of mental
distress, their sense of self and the family member who experienced mental distress, and
how they made meaning of their experiences. After collecting data through one-on-one,
semistructured interviews, I analyzed the data using Giorgi’s (2009, 2012) descriptive
phenomenological method and described the research participants’ experiences.
Conducting the qualitative research study using a phenomenological approach allowed
me to uncover the intricacies and dimensions of living with another person’s mental
distress from participants’ perspectives (see Qutoshi, 2018).
Participants’ accounts provided insights into their day-to-day lives with a family
member experiencing mental distress, whether a mother, father, or sibling. First,
participants described their experiences as unpleasant, overwhelming, and even
unexpected. Second, participants viewed mental distress as a disease of suffering and
confronted despair and hopelessness inherent to living with member distress in their
family. Third, mental distress affected participants’ lives beyond the emotional pain or
suffering they endured. They confronted instability, physical and emotional exhaustion,

damage to family relationships, and financial challenges. Fourth, participants coped with
the effects of mental distress by drawing strength from support from other family
members. Religion and spirituality were also integral to participants’ day-to-day coping.
They relied on their faith and spiritual practices for stability and meaning to adjust to
mental distress in the family.
Participants’ experiences living with family members’ mental distress in the faith
community were also diverse. Some participants found support in their faith community;
however, many viewed their faith community as unwelcoming, unsafe, and unreliable.
The faith communities did not have the structure and support services to accommodate
participants’ needs, which disrupted their participation and fellowship with members of
the faith community. Participants expressed their hopes to see the faith community
become a welcoming place for families and individuals living with mental distress.
In this chapter, I summarize and interpret the study findings in comparison with
the existing literature on Evangelical Christians’ mental distress experiences. The chapter
also includes a discussion of the study’s limitations and recommendations for further
research. Finally, I expound on the potential impact of the study findings in advancing
change in counseling education and beyond.
Interpretation of the Findings
For this qualitative study, I recruited eight Evangelical Christian participants and
conducted semistructured, one-on-one interviews to gain insights into the unique features,
challenges, and needs of their experiences living with or having lived with the mental

distress of a family member. I used Giorgi’s (2009) descriptive phenomenology method
to explore and describe participants’ experiences. I selected this method because I wanted
to obtain a firsthand account and knowledge of what it meant for participants to live with
a family member’s mental distress as people of faith from an Evangelical framework or
worldview. Particularly, this method allowed me to analyze the data obtained and
describe the psychological structure and shared essence of the participants’ experiences
of living with a family member confronting mental distress in their homes and faith
communities (see Creswell & Poth, 2016; Giorgi, 2009, 2012; Giorgi & Giorgi, 2003).
The findings are represented in seven themes and 19 subthemes developed from
participants’ narratives.
Theme 1: An Unpleasant and Overwhelming Experience
The first theme, an unpleasant and overwhelming experience, captured
participants’ initial reactions to a novel but destabilizing phenomenon: mental distress in
the family. All eight participants recognized the turmoil and instability mental distress
introduced into family functioning, confirming what exists in the literature that mental
distress destabilizes family functioning producing uncertainty, confusion, anxiety, stress,
and taxing needs (see Crowe & Lyness, 2014; Liegghio, 2017; Saunders & Byrne, 2002).
Participants felt overpowered, highlighting how mental distress in the family was
disorienting, throwing the family into disorder at its onset. Many participants witnessed
the rapid decline in the well-being of the family member experiencing mental distress,
compelling them to make unexpected and painful decisions to hospitalize or seek

psychological support. Participants had to overcome their initial despair and
hopelessness, adjust to the sudden changes in functioning, and manage stressful daily
demands to care efficiently for the mental health needs of the family member.
Theme 2: A Disease of Suffering
Participants described the suffering of their family member who was struggling
with mental distress next to their own suffering from living with mental distress in the
family. Everyone living with or near a person with mental distress suffers. Rogers et al.
(2012) acknowledged that suffering existed in families with mental distress; however,
participants’ descriptions of mental distress went beyond viewing suffering as a
byproduct of mental distress. Participants viewed suffering as an essential feature of
mental distress, not just a product of living with mental distress. Suffering seemed
inescapable for all participants, so the second theme that emerged from this study
underscored participants’ perceptions of mental distress as “a disease of suffering.”
Indeed, the definition of mental distress by the APA (2013, 2020) states that suffering is
intrinsic to mental distress experiences, associating mental health with pain or despair.
Theme 3: The Costs of Living With Mental Distress in the Family
Mental distress in the family adversely influenced vital aspects of participants’
lives and functioning. All participants reported being affected by the mental distress in
the family, corroborating the view that the family is an emotional unit and a change in
one aspect of its structure impacts the whole family system (see Kerr & Bowen, 1988).
Participants in this study were either a parent, a spouse, or a sibling of someone

experiencing mental distress, so they all suffered from mental distress in the family,
whether it involved despair or a decline in their quality of life (see Crowe & Lyness,
2014; Fekadu et al., 2019), loss of intimacy, the breaking down of relationships (see
Liegghio, 2017; Sporer & Toller, 2017), or confronting financial stress (see Lin et al.,
2018; Rodríguez-Meirinhos et al., 2018).
All eight participants witnessed stress in their lives. Whether it is in suffering
alone or living with uncertainty, no one participant was spared by the short- and longterm
effects of living with mental distress in the family, affecting their social lives and their
psychological, physical, and spiritual well-being (see Fekadu et al., 2019; Richardson et
al., 2013). While Eaton et al. (2016) found that mothers of children with mental distress
had a negative self-perception as bad parents, participants in this study showed pride in
their children and their parenting efforts; nevertheless, the participants grieved the likely
loss of their children’s futures and dreams. Even so, participants labored diligently to
maintain order in their homes and engage in unpredictable, day-today activities (see
Richardson et al., 2013).
Participants who lived with their siblings’ mental distress experienced role shifts
and became caretakers. Like Lukens et al. (2004), Liegghio (2017), and Sanden et al.
(2015) highlighted, these siblings lived with stress and mental distress stigma and
reported feelings of helplessness and shame. Regardless of their relationship status with
the family member, participants in this study have learned to be flexible, watchful, and
ready to intervene and address whatever challenges the day brought.

Theme 4: Coping With the Effects of Mental Distress in the Family
Participants were disheartened at the onset of their family member’s mental
distress; however, they adjusted to living with mental distress experienced by their
respective family members over time. In stressful circumstances, participants looked for
help, sought answers, and pursued professional support, which facilitated their ability to
cope with mental distress in their homes (see Folkman et al., 1986; Folkman &
Moskowitz, 2004; Taylor & Stanton, 2007). Regarding religious coping, Crowe and
Lyness (2014) found that family cohesion and close relationships among family members
supported their adjustment to pain or stress in their lives. Participants collaborated with
other family members without mental distress and, whenever possible, with church
members to address the needs and challenges experienced.
All eight participants turned to their relationship with God and faith practices,
such as prayer, Bible reading, and church attendance, to adjust and find purpose in their
suffering and despair. Participants’ faith and religious beliefs provided them with the
means to cope and reconcile the suffering in their lives with their overall Christian
worldviews. Their religious convictions and practices facilitated the meaning-making
process necessary to live with their challenges. This finding reflected the extant literature
on coping, providing evidence that religious coping strategies positively helped
individuals manage mental distress in their families (see Pearce et al., 2016). Observance
of spiritual practices and beliefs in God played a moderating role and helped participants
adapt to taxing and stressful circumstances to navigate crises without losing control (see

Abu-Raiya & Pargament, 2015; Pargament, 2002; Pargament et al., 1998).
Adjustment is an ongoing process in families living with mental distress.
Participants in this study demonstrated strength as they accommodated the changing
mental health needs in the family and handled the crises they faced (see Raymond et al.,
2017; Saunders, 2003). Many participants have found new purpose and meaning in caring
for the family members experiencing mental distress, meaning facilitated by their
religious beliefs. Their religious beliefs transformed their perceptions and attitudes about
mental distress and fostered a deep commitment to loving and caring for the family
member living with mental distress. Participants have become resilient in managing the
effects of mental distress in their families (see Jonker & Greeff, 2009).
Additionally, some participants faced mental distress stigma in their families and
faith communities and were often blamed for the family member’s mental distress or
accused of being enablers (see Sanden et al., 2015). Participants addressed mental distress
stigma in their families and advocated for mental health literacy as the answer to
combatting stigma in their faith communities. Participants did not associate depression or
other adverse conditions with mental distress stigma similar to Sanden et al.’s (2013)
findings. Mental distress stigma hindered participants from engaging fellow congregants
and faith leaders and limited their access to support, which was often lacking in their faith
communities. Nonetheless, participants were enterprising, advocating for their needs and
pursuing social support, often outside of their faith communities, to cope with help from

friends, mental health professionals, and social services groups or organizations (see
Sanden et al., 2013).
In their seminal study about Evangelical Christians in faith communities, Rogers
et al. (2012) did not examine how families living with mental distress coped. They did
not focus on the mental health needs or other challenges Evangelical Christians faced and
their implications for their participation in the faith community. The current findings
accomplished that. The current study findings illuminated the coping mechanisms and
meaning-making processes that allowed participants to adjust to mental distress in their
families and maintain productive lives. For example, they loved and cared for their family
member; they remained committed to their familial responsibilities, often withstanding
strenuous daily home and work demands; they proved to be resourceful when help was
scarce; and they overcame mental distress stigma to live meaningfully. Despite the high
fiscal, emotional, and physical costs of living with mental distress, some participants
reported personal and spiritual growth, which appeared to result from their coping
successfully with mental distress in their family.
Theme 5: A Supportive Community
From participants’ accounts, the faith community was supportive when they could
freely talk about their struggles with mental distress. A supportive faith community was
the place participants found love and care from other members as they shared their
struggles with mental distress in their families. Participants also felt supported when faith
leaders publicly discussed mental distress and acknowledged families and individuals

living with mental distress in the faith community. In general, participants who perceived
their faith community as supportive described it as a place they found assistance to meet
their mental health needs. Sometimes, their needs were spiritual, social, moral, and/or
financial. This finding supported Dyess and Chase’s (2010) view that faith communities
are places where members can find caring social and spiritual support, hence, a faith
community is a resource for its members. It is where they find acceptance, and loving,
and caring relationships in times of distress (see Gailliard & Davis, 2017; Krause, 2009;
Merino, 2014). Being heard and feeling understood and supported contributed to
participants’ satisfaction, thus strengthening their connection to the faith community (see
Obst & Tham, 2009).
Theme 6: An Unwelcoming, Unsafe, and Unreliable Faith Community
All eight participants turned to their faith communities in times of need, indicating
their preference for the faith communities to be a source of information about mental
distress and mental health support services (see Bornsheuer et al., 2012; Rogers et al.,
2012). However, participants faced several hurdles in the faith communities.
Participants’ preferences for support from within their faith communities justified their
disappointment in their faith leaders and fellow congregants because their accounts
portrayed their faith communities as unwelcoming, unsafe, and unreliable.
Participants’ experiences revealed faith communities that lacked funding for and
investment in mental health services (see Rogers et al., 2012; Stetz et al., 2011; Wong et
al., 2018). Participants also encountered reluctance or indifference from faith leaders who

seemed uninterested in the mental health conditions of those they served or were
unwilling to be involved and walk alongside individuals living with mental distress in
their family.
Faith leaders also seemed to have priorities that competed with participants’ needs
and mental health concerns. For example, faith leaders seemed to have prioritized church
attendance or spiritual needs over compromises to accommodate families or individuals
living with mental distress during church services. Church programming did not
incorporate the mental health conditions and concerns of participants’ family members.
Participants’ expectations were incongruous with the daily experiences and concerns of
fellow congregants and faith leaders. This lack of familiarity with mental health
challenges might explain the lack of empathy and support from the faith leaders that
affected participants’ experiences of mental distress (see Baldwin & Poje, 2020; Freeman
& Baldwin, 2020; Rogers et al., 2012; Wesselmann et al., 2015).
The lack of knowledge about mental distress in the faith community and the
stigmatizing attitudes participants witnessed disrupted their connection and relationships
with fellow congregants, furthering their alienation (see Rogers et al., 2012; Stetz et al.,
2011; Wesselmann et al., 2015; Wesselmann & Graziano, 2010). Participants did not
receive the compassion, support, and mental health resources they expected from within
their faith communities (see Baldwin & Poje, 2020; Rogers et al., 2012; Stetz et al., 2011;
Wong et al., 2018); consequently, many participants had difficulty feeling included or
fully participating in their faith community (see Brinkley & Kaul, 2014; Corrigan, 2020;

Lloyd & Waller, 2020; Stetz et al., 2011). Not having the social and spiritual support they
needed and facing the lack of mental health services, some participants preferred leaving
rather than staying in a faith community in which fellow congregants did not value them
and address their needs (see Lloyd & Waller, 2020; Rogers et al., 2012; Stetz et al., 2011;
Wesselmann et al., 2015; Wesselmann & Graziano, 2010). Far from being a place of
connection, the faith community became an unwelcoming and isolating place for some
participants (see Webb et al., 2011).
Participants’ disappointment with their faith community, its leaders, and fellow
congregants seemed to involve the sense of abandonment they felt. Participants longed
for their faith leaders and other congregants to be a part of their journey with mental
distress. Other members in the faith community appeared unprepared or unwilling to
embrace its members living with adverse mental health conditions in their midst.
Participants felt invisible and believed their needs were dismissed or ignored.
Theme 7: High Expectations for Leaders and Congregants
Participants in this study expressed their desire or expectations for a more
supportive faith community for families and individuals experiencing mental distress.
These expectations were not mere hopes for a welcoming faith community but resulted
from participants’ disappointment with their faith communities. Participants longed for a
compassionate faith community where families like theirs would find acceptance rather
than blame or judgment.

There is evidence in the literature that causation beliefs about mental distress
influenced congregants’ experiences of mental distress in faith communities (see Lloyd &
Waller, 2020; Wesselmann et al., 2015). Although it was the case in this study,
participants mainly attributed the unpleasant experiences, lack of support, and lack of
empathy to mental health illiteracy or ignorance. Some participants reported that their
faith leaders had either experienced mental distress or had someone with adverse mental
conditions in their family; consequently, participants who felt blamed for the mental
distress in their families were hesitant to seek support or gave up trying. Some
participants were content with superficial connections with fellow parishioners. Others
were hurting in isolation or seeking community and support away from their faith
communities.
By majority (n = 7), participants believed an increased knowledge about mental
health and awareness of mental distress could significantly contribute to addressing their
needs and improving their participation in the faith community. From the participants’
perspectives, mental health illiteracy in the church was detrimental to their spiritual,
social, and emotional well-being. It also contributed to mental distress stigma.
Participants encountered indifference or dismissal of their mental health needs despite the
similarity in religious beliefs with their fellow congregants. Their experiences seemed to
differ from participants in Bornsheuer et al.’s (2012) phenomenological study who found
acceptance and support in their faith communities facilitated by their shared values and
beliefs. This finding highlights a historical pattern in faith communities as parishioners

and faith leaders continue to ignore mental health needs while readily showing more
support and care to individuals suffering from physical ailments such as cancer. Sadly,
experiencing mental distress did not generate the same enthusiasm, concern, or
compassion in faith communities as medical conditions (see Putnam, 1885; Rogers et al.,
2012).
Participants who received support from fellow parishioners and faith leaders were
grateful for it; however, the support was temporary, far below the prolonged financial,
emotional, spiritual, and physical impacts of mental distress in the family. Social support
is essential to individuals living with mental distress in faith communities (see Rogers et
al., 2012); however, fellow parishioners withheld support or failed to recognize and
attend to participants’ concerns, whether intended or not. While participants expressed a
preference for long-term support, mental health illiteracy, indifference, or mental distress
stigma could explain the inadequate support participants received from members of their
faith community.
Participants understood the power of faith leaders in shaping how they
experienced living with mental distress in the faith communities. Faith leaders were
influential opinion-formers in the faith communities. Therefore, their views and decisions
affected church programming, resources allocation to church activities, and participants’
well-being. Whether the faith leaders were aware of the significance of their position and
leadership in shaping mental distress experiences, participants expected them to
champion mental health and be advocates for individuals and families living with mental

distress. With only a quarter of religious congregations disposing of structures to address
mental health challenges confronting their members (Wong et al., 2018), participants
wanted faith leaders as partners in creating an environment that supports individuals
experiencing mental distress in the faith communities.
Researcher Reflection
For this qualitative study, I selected Giorgi’s (2009) descriptive phenomenological
psychological method, which guided the research process, including constructing the
research questions, recruiting participants, collecting and analyzing the data, and
interpreting findings. The descriptive phenomenological approach to qualitative research
presumes that researchers can uncover a phenomenon’s essential structures by obtaining
rich accounts from participants who have lived through it (see Giorgi, 1997). With this
premise guiding the inquiry, I recruited eight participants living with, or having lived
with, a family member experiencing mental distress and I used semistructured
interviewing that facilitated rich descriptions of participants’ experiences. As such, using
Giorgi’s descriptive phenomenological psychological method allowed me to describe the
circumstances of participants’ experiences of living with a family member confronting
mental distress; consequently, I bracketed any predetermined knowledge of mental
distress and focused on facilitating the storytelling throughout the study (see Giorgi,
2009; Husserl, 2017).
Descriptive phenomenology influenced the data analysis as well. I focused on
describing the conditions, challenges, and effects of living with mental distress,

highlighting the psychological aspects of their experiences that they were unaware of
while refraining from interfering with or discarding meanings participants expressed (see
Giorgi, 2009, 2012). Therefore, the findings reported in this section are expressions of
participants’ perspectives of their experiences. As the researcher, I used language to
describe the main features of the experience of living with a family member with mental
distress, as they appeared to me from participants’ descriptions of their phenomenal
world (see Giorgi, 2009, 2012).
I had a limited and professional understanding of mental distress as a mental
health counselor prior to the study. I met participants who were humble, vulnerable, and
generously, willing to share their stories about how living with a family member
experiencing mental distress affected their day-to-day lives. The themes that emerged
from their accounts highlighted participants’ experiences who showed love,
determination, and commitment to their family member’s well-being despite adversity. It
was evident that while participants would not have chosen to live with mental distress in
their families, they stood courageously by their family member and fought for their
wellbeing in faith communities that were mostly indifferent to their concerns and need.
Participants’ disappointment with the faith communities was a salient aspect of their
experiences; nonetheless, they adjusted to the daily challenges to find meaning in their
suffering. Their faith in God was crucial in this meaning-making process.
Lastly, this study highlights participants’ humanity seen through the challenges
they encountered, the courage they showed, and their commitment to live productively

despite the challenges they faced. The resilience participants showed living with mental
distress in their families was inspiring. Their love and commitment to the well-being of
their family member most likely produced this resilience. It would be easy to dismiss
participants’ accounts of mental distress as human experiences or as statistics. But each
account showed a different facet of what it meant for participants to live with a family
member experiencing mental distress. That is, indeed, the strength of the
phenomenological approach to study giving each participant had a voice to tell their story
in the way they found fitting.
Limitations of the Study
This qualitative study detailed the daily experiences of mental distress of
Evangelical Christians living with mental distress in their families and church
environments. It is plausible that mental distress stigma prevented the disclosure of
certain aspects of participants’ experiences. For example, one participant was concerned
about sharing their story in ways that may identify them. I shared their concern. Still, that
participant’s story was as genuine as other participants’ accounts.
My concern about the potential for compromising interviewer-interviewee
relationship dynamics impeding the interview process did not materialize. Participants
shared their experiences as they deemed fit and were willing to be vulnerable. Still, it is
conceivable that the design of the research questions limited participants’ narration of
their experiences. Lastly, I took the necessary steps to bracket any preunderstanding of
the phenomenon so that the findings reflected the participants’ views; nonetheless, it is

still probable that my role as an observer participant affects the interviewing, data
collection, data analysis, and reporting of findings (see Patton, 2015; Shenton, 2004).
The study had a few other limitations by its design as a phenomenological inquiry
and its focus on Evangelical Christians. First, the small sample size of eight participants,
though it allowed me to reach data saturation (see Guest et al., 2006; Mason, 2010;
Ravitch & Carl, 2016), was still a limitation. I recruited participants from four different
states representing two distinct geographical regions of the United States, thus ensuring
some diversity in the sampling. Readers from different backgrounds and religious
affiliations will relate to these findings since the chief objective was to describe the
universal or general knowledge I discovered about a person living with a family member
who experienced mental distress in the context of a faith community (see Englander,
2012). Nonetheless, the sample comprising only Evangelical Christian participants
limited the scope of the findings’ transferability.
Secondly, the disproportional representation of participants’ gender and
relationship status to the family member with mental distress impacts the findings’
transferability. Of the eight participants, six were female, and two were male. Also, most
of the participants (n = 5) were parents to adult children with mental distress. Only two
participants shared experiences of their sibling’s mental distress, and one participant lived
with a spouse’s mental distress. The transferability of the findings is limited to adult
Evangelical Christians who were a parent, a spouse, or a sibling.

Lastly, the other criterion for participant selection apart from having lived with
mental distress in their family is the concept of evangelicalism. Participants’ racial,
cultural, socio-economic backgrounds, and denominational traditions were not considered
in participant selection since the intent was to describe the essence or universal features
of the phenomenon of living with a family member experiencing mental distress as an
Evangelical Christian. I have wondered if the factors mentioned above influenced the
participants’ experiences of living with mental distress in the family and faith
communities. While participants included Asians and Whites, caution is prescribed in
transferring findings to either racial group.
Recommendations
This study advanced the literature on Evangelical Christians and mental distress
by bringing greater awareness to the needs and challenges families living with mental
distress may face in two separate contexts, first in their homes and second in their faith
communities. While participation in the study gave a voice to only eight individuals to
share their experiences, there are many other Christians in various religious
denominations whose voices we must also hear. Future phenomenological researchers
can undertake similar studies with Christians who do not subscribe to Evangelicalism.
Their findings can increase mental health professionals’ competencies in working with
people of faith from diverse religious backgrounds seeking professional counseling
compatible with their religious beliefs.

Secondly, as participants in this study expressed, they valued involvement in the
weekly gathering and church services. They longed for moments and opportunities for
corporate worship. Unfortunately, those weekly worship services did not accommodate
their families’ physical, spiritual, or mental health needs. As one participant shared, their
feedback to faith leaders to improve services “somewhat fell on deaf ears,” thus
furthering their feelings of isolation.
Belonging and feeling connected to one’s faith community has many mental
health benefits for congregants, including social support, acceptance, and improved
wellbeing (see Freeze, 2017; Hayward & Krause, 2015; Obst & Tham, 2009). More
studies are needed to explore the relationships between faith leaders and individuals or
families living with mental distress. Understanding factors that explain faith leaders’
unwillingness or lack of interest in incorporating feedback from families and individuals
living with mental distress can help; thus, research findings that provide information to
faith leaders and enable them to facilitate families living with mental distress’ connection
with their faith communities may increase their participation in the faith community’s life
and improve their mental health.
Third, most researchers who studied mental distress in the faith community have
called for a collaborative relationship between clergy and the mental health community to
enhance mental health literacy and access to treatment (see Baldwin & Poje, 2020;
Rogers et al., 2012; Sullivan et al., 2014; Vermaas et al., 2017). This study provided
further evidence for educating all congregants in the faith community about mental health

conditions. I agree that such cooperation can enhance faith leaders’ mental health
literacy, positively affecting parishioners’ mental distress experiences; however, this
study’s findings revealed that some faith leaders failed to provide the necessary support
that congregants with mental distress need despite their awareness of mental distress and
personal experiences with mental distress. More studies exploring Evangelical Christian
leaders’ experiences of their congregants’ mental distress can furnish compelling details
about how they process and engage it to provide mental health services or support to
those who need them.
Lastly, I did not consider the impact of participants’ racial, gender, and cultural
backgrounds on the study. Additionally, I did not consider the racial or ethnic
composition of their faith communities represented in this study. Future researchers can
design studies considering these other dimensions of participants’ mental distress
experiences, which I presume may increase counselors’ familiarity and sensitivity with
mental distress experiences in faith communities.
Implications
The goal of this study was to understand the overall experience of Evangelical
Christians living with a family member facing mental distress in their home and faith
communities. The findings highlighted several potential opportunities to promote positive
social change for people represented in the study sample, mental health professionals, and
faith leaders. First, participation in this study gave a voice to participants to break the
silence about their mental distress experiences and reach a wider audience. One

participant said, “the most hurtful thing is that we can’t share it with them.” I was
privileged to be a witness to their pain as they recounted their experiences, but also
courage and devotion to their family member with adverse mental health conditions.
Also, I hope participation in the study was healing as I facilitated and listened to the
telling of their stories. Perhaps this study’s findings will advance conversations about
mental distress in faith communities to reduce mental distress stigma.
The findings of this current study underscore the need for counselors and
counselor educators to familiarize themselves with Evangelical Christians’ challenges
and concerns regarding living with a family member experiencing mental distress. All
participants in this study sought mental health counseling for themselves or their family
members with mental distress. The results can enhance counselors’ readiness to work
effectively with such clients, becoming culturally informed and providing culturally
sensitive treatment when working with Evangelicals Christians with mental distress in
their families.
Counselors working with Evangelical Christians in similar conditions to this
study’s participants will have adequate information in their therapeutic work. Counselors
can help them meet their mental health needs. They can also help them address concerns
such as disappointment with the faith community, separation from fellowship, suffering
in isolation, a crisis of faith, mental distress stigma, inadequate resources, lack of support,
broken family relationships, loss, and grief accompanying mental distress, and physical
and emotional stress. Third, the study’s findings present professionals in the mental

health community with valuable information about the influence of faith leaders in
shaping participants’ mental distress experiences. Any long-term positive change to
support individuals living with mental distress in faith communities requires
collaboration with faith leaders.
Fourth, the findings provide firsthand knowledge to faith leaders. Participants in
this study expressed their disappointments but their hopes as well for supportive and
empathic communities that accommodate them living with adverse mental conditions of a
family member; thus, findings can increase faith leaders’ awareness of the needs and
concerns impacting individuals and families living with mental distress in the faith
communities. The results can help faith leaders increase their knowledge about mental
distress. They can use these findings to develop and implement strategies to support
families living with mental distress by allocating appropriate resources to provide
physical, psychological, and spiritual support to affected families and implementing
restorative church programming.
Fifth, fellow congregants can also benefit from this study’s findings. As they learn
about participants’ day-to-day challenges and needs, they may develop and show
empathy to individuals living with mental distress in their family. Fellow congregants can
offer continuous support beyond the crisis or onset of mental distress, listening to
families and individuals, showing care and kindness in their suffering, and reaching out to
offer whatever assistance they can afford. As participants described, the effects of mental
distress can be lifelong.

Lastly, counselor educators will also find the findings valuable in training future
counselors to be culturally sensitive to elements of religion and spirituality in Evangelical
Christians’ experiences of mental distress. Researchers have explored stigma in mental
health professionals (see Charles, 2013; Francis et al., 2020). Furthermore, religious
clients distrust mental health professionals because of the pathologizing of religious
beliefs (see Harris et al., 2016; Judd & Vandenberg, 2014; Nakash et al., 2019). This
study’s findings underlying the humanity of participants in their suffering and challenges
provide helpful information to train prospective counselors to be sensitive to participants’
mental health and spiritual needs.
Conclusion
In this study, I explored the phenomenon of living with a family member
experiencing mental distress in the home and faith community. In their groundbreaking
study, Rogers et al. (2012) examined this topic quantitively. But I conducted a
phenomenological study focusing on Evangelical Christians’ day-to-day experiences
living with a family member confronting mental distress through the lens of their
religious beliefs and membership in a faith community. I aimed to take an in-depth look
at how living with a family member experiencing mental distress affected their day-today
lives, their views and attitudes about mental distress, and how they made meaning of their
experiences. I formulated one main research question and two subquestions to explore
these areas of interest. Then, I recruited and interviewed eight participants who offered
their genuine narratives of living with mental distress in the home.

The results from this current study showed long-term adverse effects mental
distress brought into the family, disrupting daily functioning and relationships. Mental
distress in the family upended lives. All participants made remarkable efforts to adjust
their expectations to be as flexible as necessary to maintain functioning. Mental distress
in the family inflicted overwhelming and lasting suffering on all family members,
including the individual with mental distress. For the participants, living with mental
distress in the family meant suffering. Their lives were constantly on alert, averting or
addressing crises, one after another; thus, they paid high emotional, physical, financial,
and spiritual costs they could not have anticipated.
Participants sought psychiatric and professional mental health treatments. Most
participants expressed satisfaction with the professional support and treatment they
received. Participants also desired assistance within their faith communities; however,
their views of their faith communities were less optimistic. Indeed, most participants did
not find the welcoming and supportive faith community they expected. Instead of
empathy and support services, most participants described faith community members as
unaware of their experiences and faith leaders unwilling to listen and engage them in
meaningful ways. As a result, many participants could not fully engage in fellowship with
the faith community members, fearing judgment and blame for the mental distress in their
families. Confronting a lack of assistance and mental health programming in their faith
communities, most participants relied on support from mental health professionals and

organizations such as NAMI; nonetheless, they found meaning in their experiences
through reliance on God and their spiritual beliefs and practices.
The study included several noted limitations; however, undertaking such a study
added to the extant literature about Evangelical Christians and mental distress. Findings
showed that mental distress was taxing and life-altering for Evangelical Christians who
participated in this study. They adjusted, having learned to cope, and live with the
adverse impact of mental distress. Their most significant disappointment was the lack of
empathy and support from their faith communities.

