


PERCEIVED HEALTH STATUS, SOURCE OF CARE AND
HEALTH OUTCOMES OF INDIVIDUALS WITH SELF-
REPORTED MENTAL DISORDERS
CHAPTER I Introduction
In Healthy People 2010, mental health is listed as a major public health concern
due to the alarming increase of the number of individuals who suffer from mental
disorders. Mental disorders are treatable. However, health disparities in the treatment of
mental disorders remain an issue because mental disorders are superficially
acknowledged and the number of mental health specialists is inadequate (National Center
for Health Statistics, 2010). According to the 2004 U.S. Census, an estimated 57.7
million Americans or about 26.2% of the total residential adult population have a
diagnosable mental disorder (National Institute of Mental Health, 2010).
Untreated medical conditions and lack of attention to modifiable risk factors are
reported as causes of an increase in serious morbidity and mortality rates among
individuals with mental disorders. The medical conditions that have been implicated in
the increased mortality rate among individuals with mental disorders are cardiovascular
disease, diabetes, respiratory disease and infectious diseases. Lack of access to health
care due to poor coordination between mental health and physical health care providers is
another contributory factor in the increased rate of morbidity and mortality among
individuals with mental disorders (Parks, Svendsen, Singer, & Foti, 2006).
Smoking has been associated with mental disorders resulting in high rates of
morbidity and mortality among individuals who smoke and have mental disorders.
1

2
Tobacco control efforts were suggested as ways to address both physical and mental
status of individuals who smoke and have mental disorders (Lawrence, Mitrou &
Zubrick, 2009).
Consistently, from 1996 to 2006, mental disorders were the top five most costly
health conditions and accounted for the largest percentage increase in the number of U.S.
civilian non-institutionalized individuals (from 20 million to 40 million people). Medical
expenses for mental disorders among the U.S. civilian non-institutionalized population
rose from $19.3 million to $36.2 million per year (Olin & Rhoades, 2005; Soni, 2009).
Individuals with mental disorders often have unmet service needs for both mental
health and physical health care (Barrio et al., 2008; Garrett & Yemane, 2006; Palinkas et
al., 2007). Lack of a regular source of health care is a critical issue for individuals with
mental disorders. Primary care physicians have difficulty in referring their patients for
mental health/substance abuse services resulting in misdiagnosed, underdiagnosed,
mistreated or untreated individuals (Shepherd, 2009).
Numerous studies have been conducted on access of mental health care and
mental health service use for those individuals with mental disorders but few studies have
been done on access to physical health care (Tsay et al., 2008). Currently, only a few
studies comparing the differences of usual source of care (USC) between adult
noninstitutionalized individuals with mental disorders and adult non-institutionalized
individuals without mental disorders have been reported. Similarly, studies comparing
differences of perceived health status between individuals with mental disorders who
have usual source of care and those who do not have usual source of care are limited. It is
important to identify factors related to the lack of a usual source of care by adult
noninstitutionalized individuals with mental disorders in order to address the service

3
disparity. Therefore, a study that primarily focuses on usual source of care and perceived
health status of individuals with mental health disorders is needed, relevant, timely and
appropriate.
Statement of the Problem
Mental health is a major public health problem in the United States because of the
increasing mortality and morbidity rates associated with mental illness (Prevention
Institute, 2009). Individuals with mental disorders have two to three times higher
mortality rate compared to those without a mental disorder (Muller-Oerlinghausen,
Berghofer, & Bauer, 2002). Smoking, alcohol consumption, lack of exercise and poor
nutrition are indicated as modifiable risk factors that put individuals with mental disorder
at a higher risk for morbidity and mortality (Parks et al., 2006).
Individuals with mental disorders face health disparities related to costly medical
expenses. Differences by race, ethnicity, age, income, gender and geography, affect the
fair allocation of resources among individuals with mental disorders. These disparities in
mental health have a great impact on the health status of individuals with mental
disorders (Quill, 2001).
The existence of health care disparities has greatly affected the health status of
individuals with mental disorders. High co-morbidity of physical and mental health
conditions, inadequate access to health care, and service fragmentation among the mental
health and physical health service delivery systems are some of the challenges faced by
individuals with mental disorders (Gill, Murphy, Zechner, Swarbrick, & Spagnolo, 2009).
Morbidities and mortalities among individuals with mental disorders will
continually increase if health care disparities are not properly addressed. The relationship
between access to care and perceived health status has not been well established

4
(McGuire, Gelberg, Blue-Howells, & Rosenheck, 2009). Exploring the demographic
factors of individuals with mental disorders in relation to their usual source of care and
how they perceive their physical and mental health status provides insight into
understanding factors that contribute to health disparity in this population. Understanding
the health care disparities particularly differences in the usual source of care and its
relationship to physical and mental health status is vital in developing and implementing
health care interventions and policies to properly provide needed services for individuals
with mental disorders (Studts, Stone, & Barber, 2006; Wiechelt, Delprino, & Swarthout,
2009; Xiao & Barber, 2007).
Statement of Purpose
The purpose of this exploratory study was to examine factors that affected health
outcomes of persons with mental disorders. This purpose was actualized by the
exploration of two specific aims. The first specific aim (A1) was to examine the
relationships of population characteristics (predisposing factors and enabling resources)
health behaviors (health services use and health practice) and health outcomes (physical
health status and mental health status). The second aim (A2) was to determine the
differences in the usual source of care and health outcomes between individuals with self-
reported mental disorders and individuals without mental disorders. Understanding these
relationships and differences provides a better understanding about health conditions, the
usual source of care, and the health behaviors associated with the health outcomes of
individuals with self-reported mental disorders. Through this understanding, strategies to
address issues regarding access to usual source of care faced by individuals with mental
disorders can also be recommended.

5
Significance to Nursing
The study sought to examine the relationships of mental disorder, usual source of
care and health status as well as the differences in the usual source of care and health
outcomes between individuals with self-reported mental disorders and individuals
without mental disorders. The findings of this study provide an increased awareness of
the issues related to usual source of care, health care services use, perceived health status
and health outcomes of individuals with mental disorders. The results of this study
reinforce the need for advocating for mental health policies and integration of health care
services for both mental and physical health needs among individuals with mental
disorders.
Research Questions
To examine the specific aims, the following research questions were addressed: o
Aim 1 Research Question 1 (A1R1): What is the relationship of population
characteristics [(predisposing factors{health conditions (mental disorders,
physical illness, co-morbid mental disorders and physical illness)},
demographic factors {age, gender, race, ethnicity, education, marital status},
socio-economic status {poverty status}, health attitudes and perceived health
status {perceived health status, perceived mental health status}), enabling
resources (usual source of care {provider type}, health care practitioner’s
characteristics {health care practitioners’ gender,
race and ethnicity}, personal/family resources {insurance status}, and
community resources {usual source of care location and
transportation mode})] and health behaviors (health services use

6
{office-based clinic visits and outpatient hospital-based clinic visits}
and health practice {smoking habit})?
oAim 1 Research Question 2 (A1R2): What is the relationship of
population characteristics [(predisposing factors {health conditions
(mental disorders, physical illness, co-morbid mental disorders and
physical illness)}, demographic factors {age, gender, race, ethnicity,
education, marital status}, socio-economic status {poverty status}, health
attitudes, and perceived health status {perceived health status, perceived
mental health status})], and health behaviors (health services use
{officebased clinics visits, outpatient hospital-based clinics visits} and
health practice {smoking habit}) controlling for selected moderating
factors, enabling resources (usual source of care {provider type}, health
care practitioner’s characteristics {health care practitioners’ gender, race
and ethnicity and provider type}, personal/family resources {insurance
status} and community resources{usual source of care location and
transportation mode})?
oAim 1 Research Question 3 (A1R3): What is the relationship of
population characteristics [(predisposing factors{health conditions (mental
disorders, physical illness, co-morbid mental disorders and physical
illness)}, demographic factors {age, gender, race, ethnicity, education,
marital status}, socio-economic status {poverty status}, health attitudes,
and perceived health status {perceived health status, perceived mental
health status}, and enabling resources (usual source of care {provider

7
type}, health care practitioner’s characteristics health care practitioners’
gender, race and ethnicity}, personal/family resources {insurance
status},and community resources {usual source of care location,
transportation mode})], health behaviors (health services use {officebased
clinic visits, outpatient hospital-based clinic visits}, health practice
{smoking habit}), and health outcomes (physical health status {physical
component summary} and mental health status {mental component
summary})?
oAim 1 Research Question 4 (A1R4): What is the relationship of
population characteristics [(predisposing factors (health conditions
{mental disorders, physical illness, co-morbid mental disorders and
physical illness}, demographic factors {age, gender, race, ethnicity,
education, marital status}, socio-economic status {poverty status}, health
attitudes, and perceived health status {perceived health status, perceived
mental health status})], health behaviors (health services use {office-based
clinic visits, outpatient hospital-based clinic visits}and health practice
{smoking habit}), and health outcomes (physical health status {physical
component summary}and mental health status {mental component
summary}) controlling for selected moderating factors [enabling resources
(usual source of care {provider type}, health care practitioner’s
characteristics{health care practitioners’ gender, race and ethnicity},
personal/family resources {insurance status} and community resources
{usual source of care location and transportation mode})]?

8
oAim 2 Research Question 1 (A2R1): Is there a significant difference in
usual source of care between individuals with self-reported mental
disorders and individuals without mental disorders?
oAim 2 Research Question 2 (A2R2): Is there a significant difference in
physical health status between individuals with self-reported mental
disorders and individuals without mental disorders?
oAim 2 Research Question 3 (A2R3): Is there a significant difference in
mental health status between individuals with self-reported mental
disorders and individuals without mental disorders?
Theoretical Framework
Overview of the Behavioral Model of Health Services Use
The Behavioral Model of Health Service Use (BMHSU) guided the development
of the specific aims of this study. The BMHSU was developed to understand, predict and
explain the means of and reasons for individual health care use. There were several
revisions and four phases of modifications that occurred since the original model was
developed in 1968 by Ronald Andersen (Andersen & Aday, 1978; Rebhan, 2010).
History of BMHSU
In Phase 1, the BMHSU had three categories namely predisposing characteristics,
enabling characteristics, and need characteristics. Predisposing characteristics include
demographics, social structure and health beliefs. Enabling characteristics include family
resources and community resources. Need characteristics include perceived needs and
clinically evaluated needs. Phase 2 of Andersen’s model was revisited in 1978. In Phase
2, the health care system and consumer satisfaction were added. The health care system

9
includes policy, resources and organization. Consumer satisfaction includes convenience,
availability, financing, provider characteristics and quality. The model was again revised
in 1980s and 1990s for Phases 3 and 4. In Phase 3, a linear relationship model emerged
with three constructs, primary determinants, health behaviors and health outcomes.
Primary determinants included population characteristics, the health care system and the
external environment. Health behaviors included personal health practices and health
services use. Health outcomes include perceived health status, evaluated health status and
consumer satisfaction. In Phase 4, the emerging model of BMHSU was developed which
composed of four main constructs; the environment, population characteristics, health
behaviors and outcomes (Andersen, 1995).
Description of the BMHSU
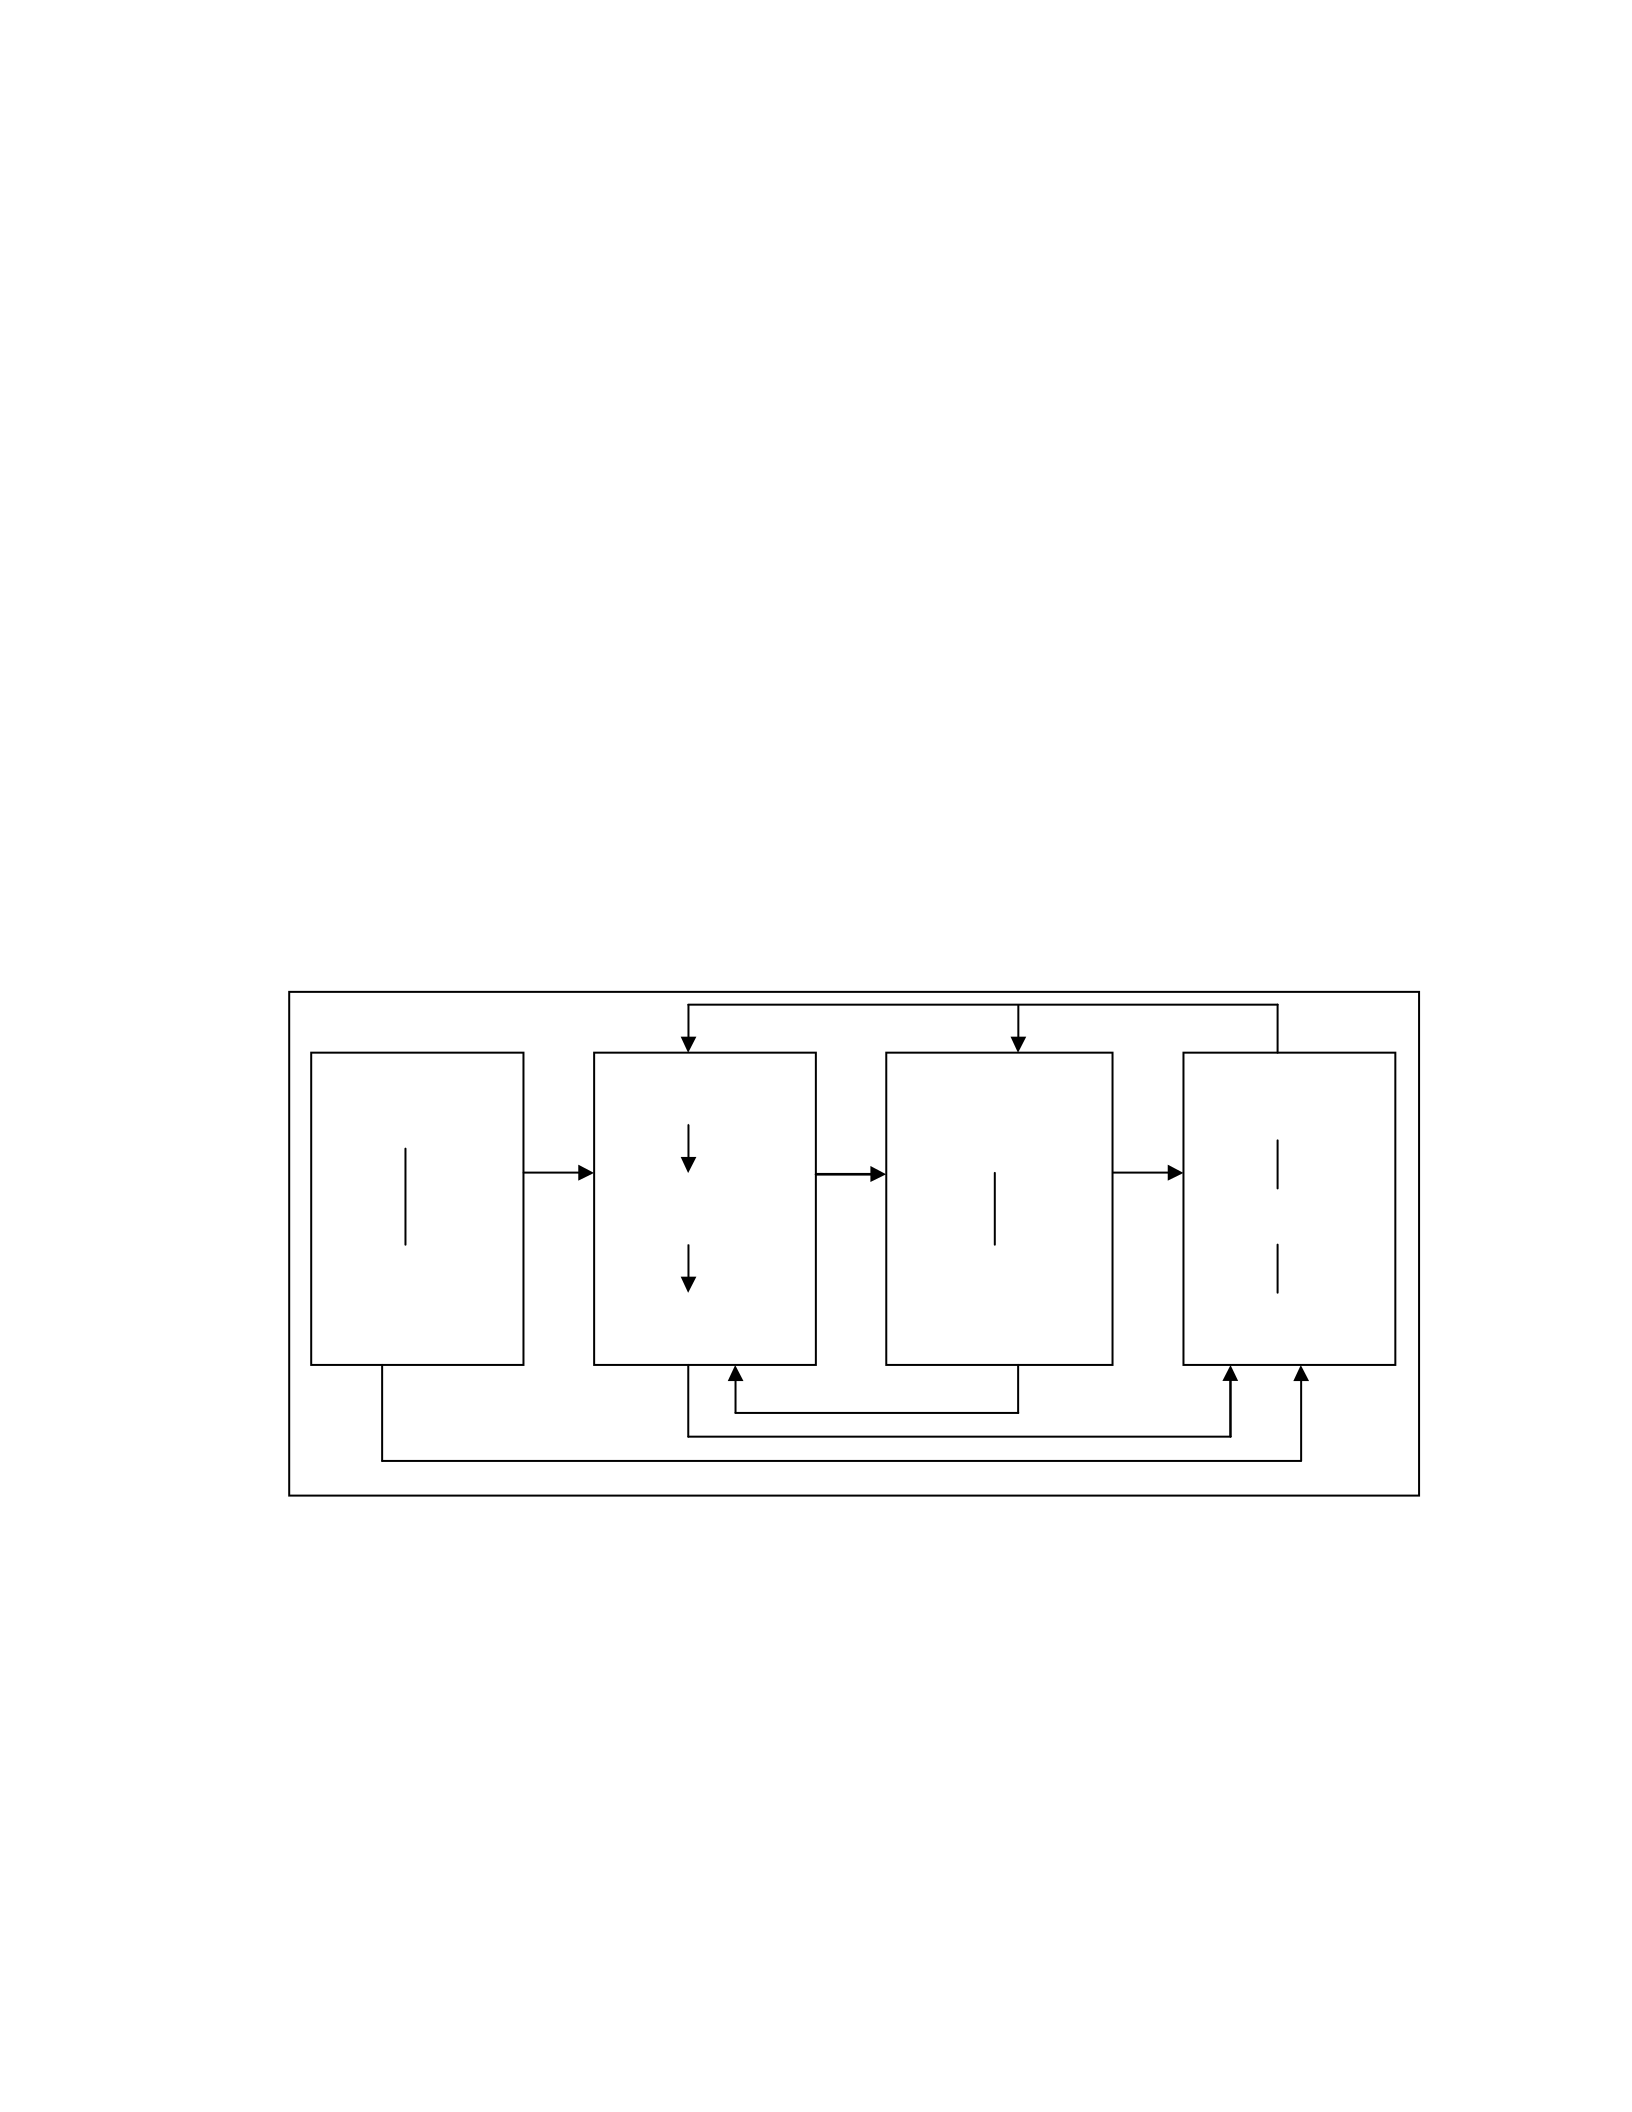
Andersen’s emerging model of BMHSU was used as a guide for structuring the
specific aims and research questions in this study. The environment consists of the health
care system and external environment. The health care system includes policy, resources
and organization. The external environment refers to the physical, political and economic
components of the environment. Population characteristics consist of predisposing
factors, enabling resources and need factors. Predisposing factors are demographic
factors, the socio-economic structure, and health beliefs. Enabling resources include
personal, family and community resources. Personal and family resources are defined as
income, health insurance, and a regular source of care. Community resources include the
various types of health care providers and types of health services organizations. The
need factors are perceived health and evaluated health. Health behavior consists of
personal health practices and the use of health services. The outcomes consist of
perceived health status, evaluated health status and consumer satisfaction (Andersen,
10
1995).
In this model, the environment influences population characteristics and
outcomes. The population characteristics influence health behavior and outcomes. Health
behavior influences population characteristics and outcomes. Outcomes in return
influence population characteristics and health behavior. Longitudinal and experimental
study designs are recommended for further exploration of this model (Andersen, 1995).
See Figure 1.1 for Andersen’s emerging model-Phase 4 Behavioral Model of Health
Services Use.
Figure 1.1 Andersen (1995) Behavioral Model of Health Services Use (BMHSU)
ENVIRONMENT POPULATION HEALTH OUTCOMES
CHARACTERISTICS BEHAVIOR
The BMHSU has been utilized in the several studies of various populations
including some vulnerable populations [e.g., individuals with panic attacks (Goodwin &
Andersen, 2002); individuals on antipsychotic medications (Jano, Johnson, Chen, &
Aparasu, 2008); adults with human immunodeficiency virus (Kilbourne et al., 2002);
homeless women (Tam, Zlotnick, & Bradley, 2008); people with mood disorders (Wu,
Erickson, Kennedy, 2009); and children with special health care needs (Kane, Zotti, &
Health Care
System
External
Environment
Predisposing
Factors
Enabling
Resources
Need
Personal
Health
Practices
Use of Health
Services
Perceived
Health Status
Evaluated
Health Status
Consumer
Satisfaction

11
Rosenberg, 2005)]. The BMHSU was useful in guiding these studies by identifying the
predictors or determinants of health service use and health outcomes among the specific
population of interests.
Gelberg, Andersen, and Leake (2000) tested the expanded BMHSU model with a
sample of 363 homeless people. In this study, the model consisted of population
characteristics, health behavior and outcomes. Population characteristics included the
three domains of predisposing factors, enabling resources and need. Consistent with the
previous models, predisposing factors consisted of demographics and socio-economic
structure. Health attitudes construct was included as one of the characteristics in the
predisposing domain. Usual source of care construct was included as one of the
characteristics in the enabling domain. Perceived health status construct was included as
one of characteristics in the need domain. Health behaviors consisted personal health
practices and use of health services. Tobacco use was included as one of the
characteristics in the behaviors in personal health practices. Outcomes consisted of health
status and satisfaction with care (Gelberg et al., 2000).
Several similarities but altered variations of the BMHSU model evolved from the
study of Gelberg et al. (2000). These similarities included the omission of environment as
a construct and inclusion of predisposing factors, enabling resources and perceived health
status as variables of population characteristics. Additionally, usual source of care was
considered as one of the enabling resources; health services use was identified as one of
the health behaviors; and tobacco use or smoking habit was indicated as one of the health
practices.
In this study, the influence of the environment on health outcomes is recognized
but the environment was not measured because the Medical Expenditure Panel Survey

12
(MEPS) study was a study conducted across the United States. The characteristics of the
environment would have been variable in different regions, making them difficult to
describe and quantify. Thus, the variables in the environment were not available in the
MEPS data source. Smoking habit was selected as a variable for health practice because
of its impact on the depressive symptoms and health outcomes of people with physical
illness (Coultas, Edwards, Barnett, & Wludyka, 2007) and the significant association of
smoking habit to poor mental health status (Jofre-Bonet, Busch, Falba, & Sindelar, 2005).
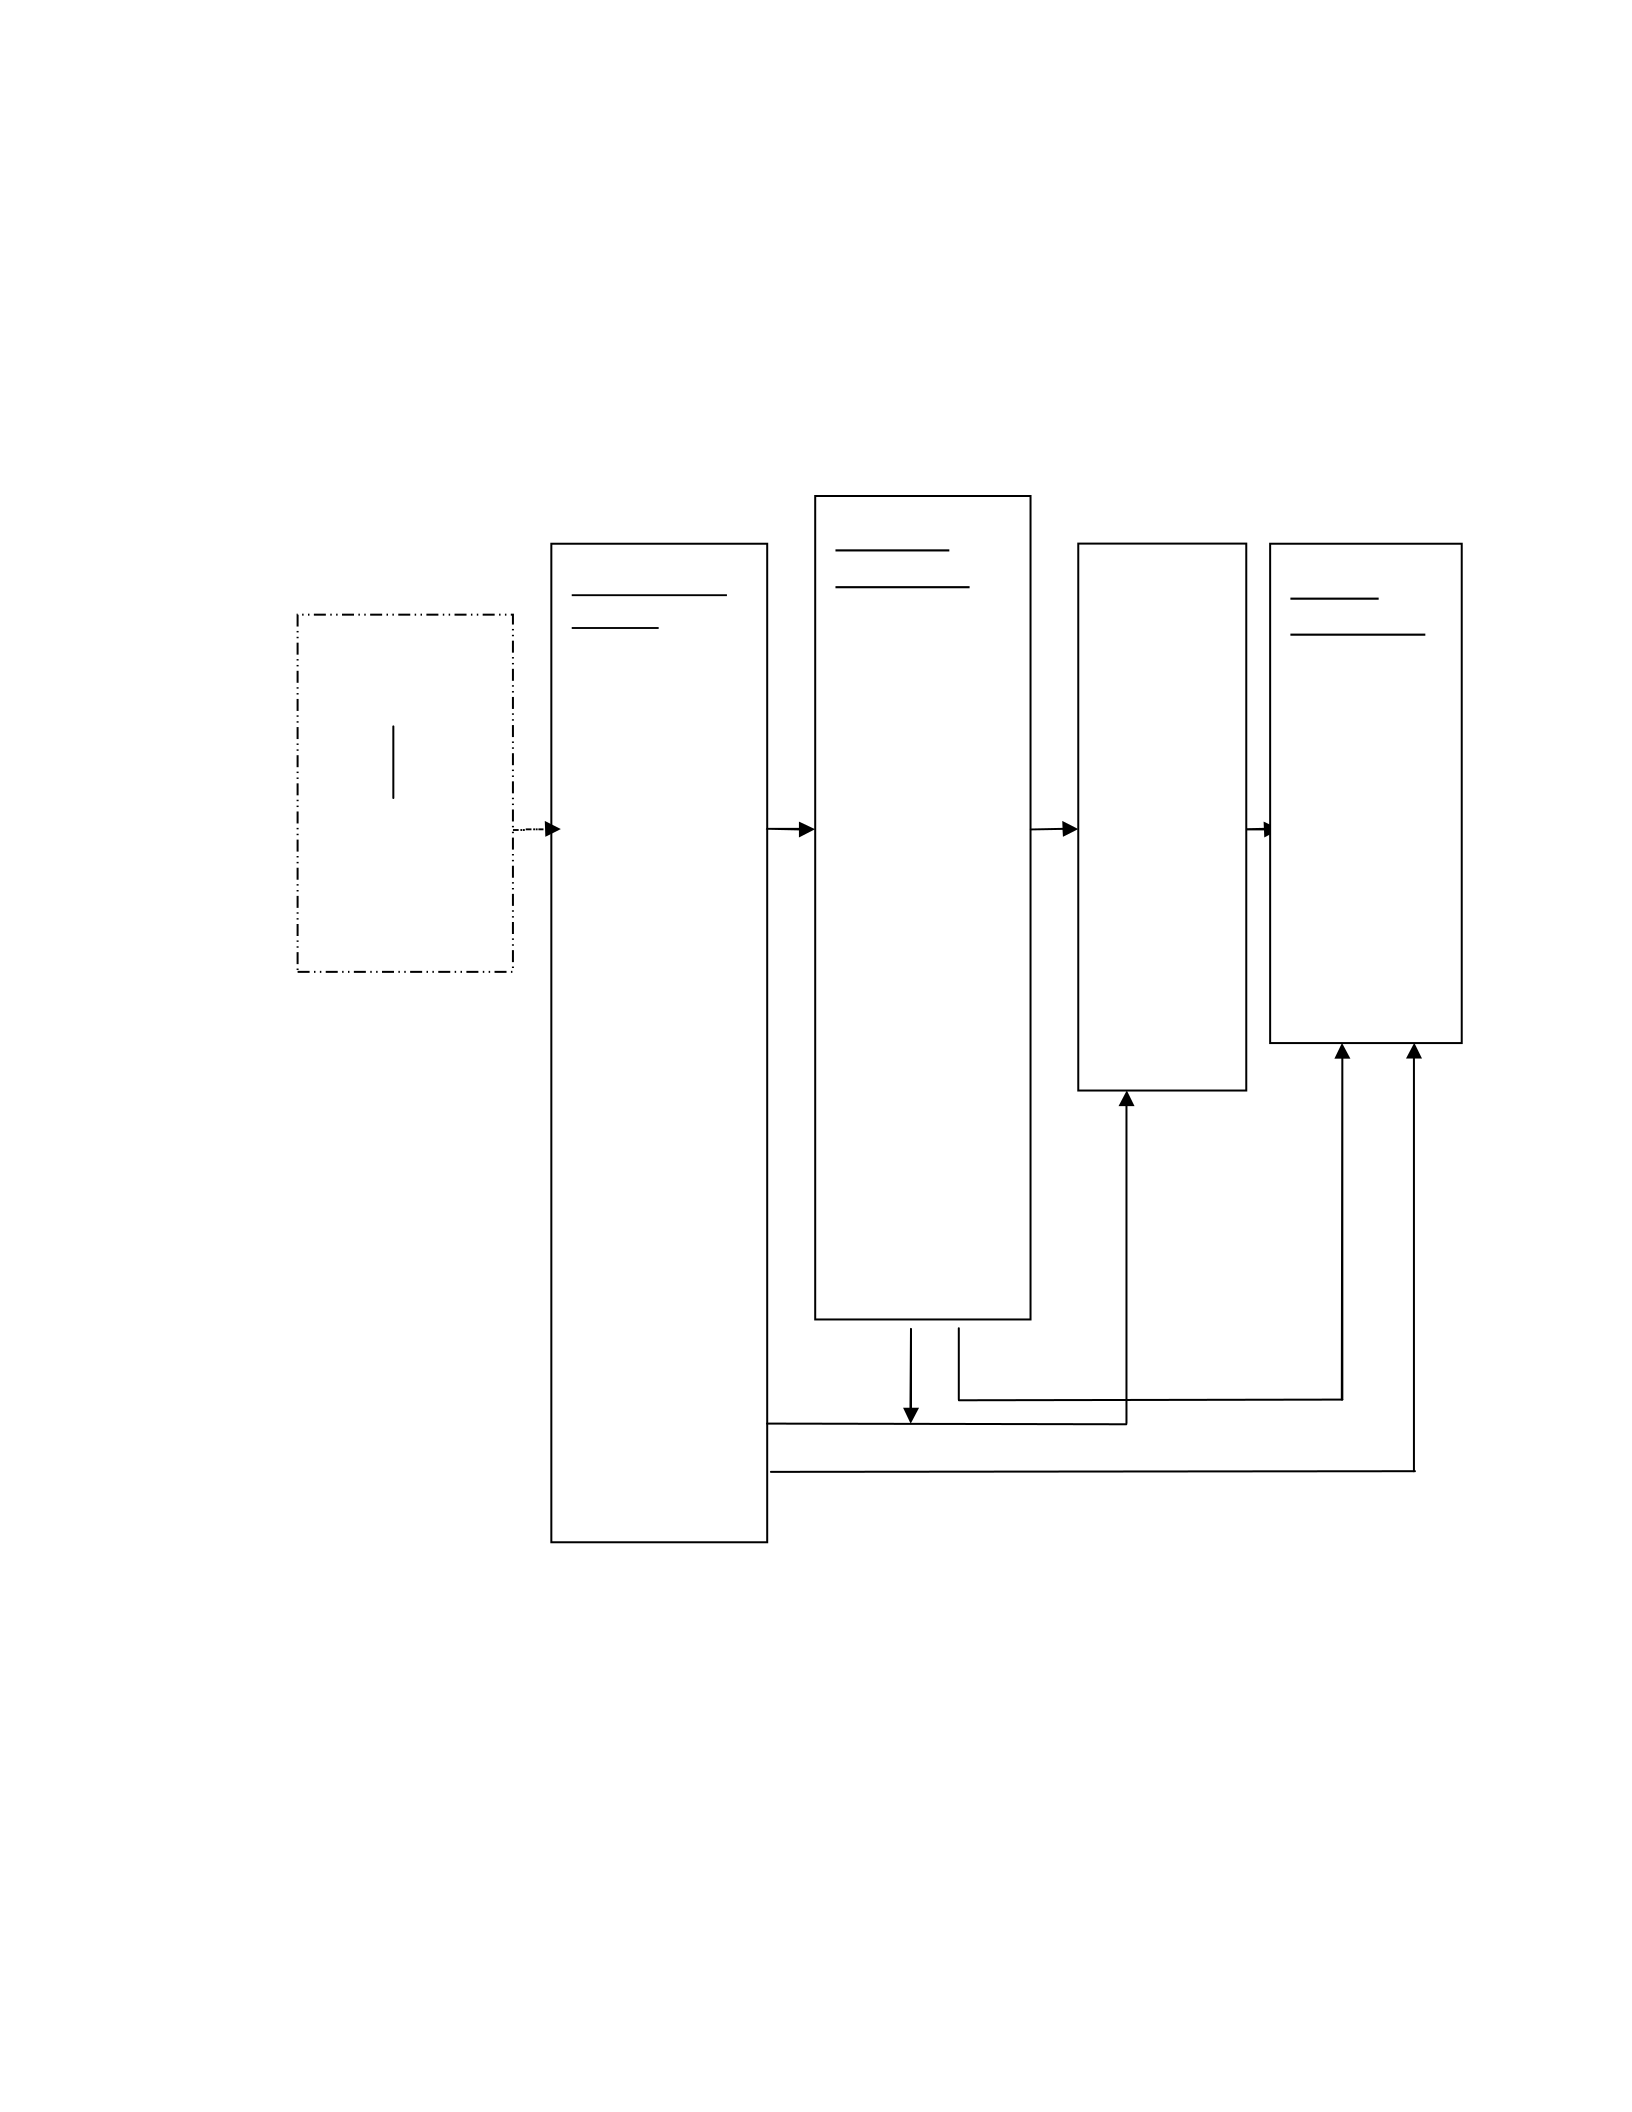
For the purpose of this study, a modified version of Behavioral Model of Health
Service Use (BMHSU) was used and is shown in Figure 1.2. The main concepts of this
study included population characteristics (predisposing factors and enabling resources),
health behaviors (health services use and health practice) and outcomes (health
outcomes). Due to the cross-sectional design of this study, feedback loops were negated
and one time linear relationships were evaluated.
In this framework, predisposing factors consisted of health conditions,
demographic factors, socio-economic structure, health attitudes and perceived health
status. Enabling resources included the usual source of care, health care practitioners’
characteristics, and personal, family and community resources. Health behaviors
consisted of health services use and smoking habit. Health outcomes consisted of
physical health status and mental health status. Predisposing factors and enabling
resources affect health behaviors and health outcomes. Enabling resources mediates
between predisposing factors and health behavior. Health outcomes are determined by
predisposing factors, enabling resources and health behaviors. The italicized constructs
(health conditions, perceived health status, usual source of care, physical health status
13
and mental health status) were the variables of interest in this study. See Figure 1.2 for
the modified BMHSU.
Figure 1.2 Modified Behavioral Model of Health Service Use (BMHSU)
ENVIRONMENT POPULATION HEALTH OUTCOMES
For A1R1, predisposing factors and enabling resources were independent
variables and health behaviors were dependent the variables. For A1R2, predisposing
factors were independent variables, enabling resources were covariates, and health
behaviors were dependent variables. For A1R3, predisposing factors, enabling resources
and health behaviors were independent variables and health outcomes are dependent
CHARACTERISTICS BEHAVIORS
Predisposing
Factors
-Health
Conditions
Mental (
Disorders;
Physical
Illness;
Co-morbid
Mental and
Physical
Illness)
-Demographic
Factors Age, (
Gender, Marital
Status, Race,
Ethnicity;
Education)
-Socio -
Economic
Status Poverty (
Status)
Health -
Attitudes
-Perceived
Health Status
(Perceived
Health Status
and Perceived
Mental Health
Status )
Enabling
Resources
- Usual
Source of
Care –
Provider Type( )
-Personal/
Family
Resources
(Insurance
status)
- Health Care
Practitioners’
Characteristics
Health Care (
Practitioner’s
Gender, Race,
Ethnicity)
- Community
Resources
Usual Source (
of Care,
Location and
Transportation
Mode)
Health Care
System
External
Environment
-Health
Services
Use
( -Office
Based
Clinic
Visits,
Outpatient
Hospital-
Based
Clinic
Visits)
-Health
Practice
(Smoking
Habit)
Health
Outcomes
-Physical
Health
Status
(Physical
Component
Summary)
-Mental
Health
Status
Mental (
Component
Summary)

14
variables. For A1R4, predisposing factors and health behaviors were independent
variables, enabling resources were covariates and health outcomes were dependent
variables.
For A2R1, health conditions were independent variables and usual source of care
was dependent variable. For A2R2, health conditions were independent variables and
physical health status was dependent variable. For A2R3, health conditions were
independent variables and mental health status was dependent variable.
Summary
Mental disorders are a treatable health concern and yet morbidity and mortality
rates continue to escalate. Issues in health conditions, health attitudes, perceived health
status, usual source of care, personal/family/community resources, health services use,
and health practice of individuals with mental disorders should be explored to facilitate
the development of strategies that improve the health outcomes of these individuals. The
purpose and specific aims of the study addressed these issues by examining the
relationships among population characteristics (predisposing factors and enabling
resources), health behaviors (health service use and smoking habit) and health outcomes
(physical health status and mental health status) of individuals with health conditions
(mental disorders, physical illness and co-morbid mental disorders and physical illness).
A dearth of studies related to disparities in mental health care and mental health services
use has been an additional concern. This study addressed some of those disparities by
determining the differences on usual source of care and health outcomes (physical health
status and mental health status) between individuals with self-reported mental disorders
and individuals without mental disorders.

CHAPTER II
Literature Review
This chapter includes a review of literature. The modified Behavioral Model of
Health Service Use (BMHSU) is used as the framework for presenting the review of
literature. The review focuses on what is known concerning the concepts of BMHSU
(population characteristics, health behavior, and health outcomes) in the context of the
individuals with health conditions (mental disorders, physical illness and co-morbid
mental disorders and physical illness).
Population Characteristics
The constructs of population characteristics include predisposing factors and
enabling resources. Predisposing characteristics include health conditions, demographic
factors, socio-economic status, perceived health status and health attitudes. Enabling
resources include usual source of care, personal and family resources, health care
practitioners’ characteristics and community resources.
Predisposing Factors
Health Conditions. Physical illnesses, mental disorders and co-morbid medical
conditions affect health behaviors such as health services utilization and smoking habit as
well as health outcomes such as physical and mental health status. Coultas, et al., (2007)
conducted a cross sectional study of 207 chronic obstructive pulmonary disease (COPD)
patients with a smoking history to detect the health impact or predictors of depression.

16
16
They found that high levels of depressive symptoms were associated with increased
physical illness related to physician visits and hospitalizations. However, the association
between high levels of depressive symptoms and emergency room visits related to
physical illness was not found to be significant. The authors also found that continued
smoking and high perceived illness were predictors of depressive symptoms and indicated
that future studies should investigate the associations between smoking and depression
among outpatients with physical illness and co-morbid mental disorder and physical
illness (Coultas, et al., 2007; Keizer, Gex-Fabry, Eytan, & Bertschy, 2009).
Individuals with mental disorders have significantly higher risk of having physical
illnesses compared to the general population. A cross sectional study of 99 clients with
schizophrenia and on antipsychotic Clozapine found that patients with a mental disorder
had more positive attitude toward their physical health even though their clinical risk
factors were above the normal parameters (e.g., above normal body mass index and waist
circumference). The authors suggested using a collaborative approach between mental
health professionals and general practitioners in monitoring the physical health status of
the clients who have mental disorders (Brunero & Lamont, 2010).
Although the study of Brunero and Lamont (2010) explored the relationship
between the predisposing factors of physical illness and health behaviors, the effect of
usual source of care, community resources and health services use among individuals with
mental disorders continues to be understudied. Furthermore, the association of health
attitudes and actual health services use has not been well established. Future research
must focus on this area of need in order to address health outcomes (Brunero &
Lamont, 2010; Jang, Chiroboga, & Okasaki, 2009).

17
Individuals with mental disorders have an increased risk of developing physical
illnesses which has an impact on health outcomes. Individuals with mental disorders are
more likely to have unhealthy lifestyles such as smoking habit which predisposes them to
hypertension or coronary heart disease (McKeown & Colman, 2006). A significant
association between health outcomes and co-morbidity of physical illness and mental
disorders exists but the mechanisms of the associations between physical conditions and
mental disorders remain unknown. In addition, there is a scant literature on these
associations so further investigation focusing on health outcomes and its associations to
physical and mental illness is warranted (Sareen et al., 2006).
Individuals with mental disorders have a high risks for having untreated physical
illnesses due to issues related to the use of health services, poor health practices (i.e.,
smoking) or negative health attitudes. Most studies have focused on the association of
health attitudes and health conditions (e.g., mental disorders and physical illness). Studies
exploring the relationships of smoking and health conditions and the effects of
predisposing factors (i.e., demographic factors, poverty status, perceived health status,
health attitudes), health services use, and health outcomes are needed to have better
understanding of disparities in health care and services use.
Demographic Factors. Socio-demographic factors, socio-economic structure and
health conditions are determinants of health services utilization (Shaikh & Hatcher,
2005). A longitudinal study by Lamkaddem, Spreeuwenberg, Deville, Foets, &
Groenewegen (2008) with Moroccan and Turkish migrants (N= 310) found ethnicity, age
and marital status were predictors of mental health status change. Age and education
were the only predictors of physical health status. Health outcomes, ethnicity and age
were predictors of health services use. Being a Moroccan was associated with a better

18
mental health status while being divorced was related to deterioration of mental health
status. Age was associated with a good mental health status but a deterioration in
physical health status. Participants with a higher education reported better physical
health status. Those who reported good mental health and physical health status used
fewer health care services. Hill et al., (2007) found that gender, age, education,
employment and socioeconomic structure were significantly associated with physical
and mental health status in individuals with arthritis (N=7,473). Individuals who were
age 55 years and above, female, unemployed and had a low socio-economic status were
more likely to report poor physical and mental health status and mental health conditions
(Hill et al., 2007).
A study conducted by Zeber and colleagues (2009) examined the associations
between patient characteristics and self- reported difficulties in accessing mental health
and general medical care services among 435 Veterans with bipolar disorder. Health care
costs and perceived difficulties in accessing medical care specialists were identified as
reasons for avoiding mental health services use. These researchers suggested integration
of mental and physical care in order to address the person’s health outcomes (Zeber,
Copeland, McCarthy, Bauer, & Kilbourne, 2009).
Racial and ethnic disparities in mental health services use remain a public health
concern as demonstrated in two studies involving youths. In the first study of 659 foster
children, researchers found that mental health services use varied among non-Hispanic
Whites, African Americans, Asian Americans and Latinos. Non-Hispanic Whites (n=314,
65%) had the highest usage of mental health services while Latinos (n=131, 46%) had the
least usage of these services across all severity categories (low, middle, high). After
controlling for confounding factors (e.g., age, sex, severity of behavior problems, and

19
mental health services need), Latinos were found to use significantly fewer mental health
services than Whites (Garland et. al., 2000).
The second study examined mental health services use among diverse sample of
youths (N=1,256) [non-Hispanic Whites (n=554, 44%), Latinos (n=332, 26%), African
Americans (n=282, 22%), and Asian Americans (n=282, 7%)]. Psychiatric diagnoses,
functional impairment, family income, and parental depression were found as predictors
of mental health services use. Non-Hispanic Whites had the highest usage in outpatient
services (i.e. specialty mental health clinics, alcohol and drug abuse treatment), 24-hour
care services (i.e. inpatient psychiatric care, residential treatment) and informal mental
health services (i.e. self-help groups, clergy counseling, peer counseling, alternative
healers) while Asians Americans had the least usage in the three types of services.
Interestingly, Latino Americans had the highest usage in informal mental health services
compared to the three racial-ethnic groups (Garland et al., 2005). Consistent in these two
studies is the racial-ethnic disparities in the use of mental health services. The highest
mental health services use were non-Hispanic Whites while the least mental health
services use were Asian Americans. Diagnoses of mental disorders and alcohol and drug
abuse, low family income, and limited mental health services were the barriers to health
services use (Garland et al., 2000; Garland et al., 2005).
Findings from a study comparing older and younger homeless adults (N=531) on
self-reported co-morbidities of mental and physical illness and usual source of care
revealed that homeless older adults were more likely to report chronic medical condition
such as hypertension and/or mental health conditions such as depression, anxiety disorder
and post-traumatic stress disorder than their younger counterparts. No information was
provided on access and use of healthcare services. Further study is needed to explore the

20
differences between the age groups on actual health services use, satisfaction with care
services, and perceived barriers to usual source care (Garibaldi, Conde-Martel, &
O’Toole, 2005).
Demographic factors can be determinants of usual source of care, health services
use and health outcomes. Studies that address the barriers to health care (i.e., lack of
access to a usual source of care, limited health care services) for persons with a mental
disorder and/or co-morbidity of an accompanied physical illness are warranted.
Socio-Economic Status. Health status and health care disparities are embedded in the
context of poverty or socio-economic status. Differences in income and poverty status that
exist among racial groups affect health services use and mental health status (Miranda,
McGuire, Williams, & Wang, 2008). Although poverty depends on the sociocultural and
political system of a particular geographical location, poverty is measured as low social
and income status, low educational status and unemployment (Patel & Kleinman, 2003).
Patel and Kleinman (2003) reviewed 11 studies on the relationship of poverty and mental
disorders. Poverty was strongly associated with poor physical health and mental disorders.
Poverty- related issues (e. g., limited access to health care resources and high health care
costs) have been associated with worsened health conditions (e.g., physical illness, mental
disorders and co-morbidity). A low level education was the most consistent indicator of
poverty. Longitudinal studies on the associations of mental disorders, physical illness and
poverty are recommended to pinpoint specific risk factors for health conditions and
address the poverty issues associated with these health conditions (Lund et al., 2010; Patel
& Kleinman, 2003).
Family income plays an important role in determining the health outcomes of
children throughout their development into adulthood. Poverty in childhood has a

21
negative effect on the child’s health that continues into adulthood. Children from
marginalized family backgrounds have an increase in physical illnesses (e.g.,
hypertension), mental disorders (e.g. depression) and premature deaths in their adult lives.
Additionally, poor children have an increased tendency to smoke and to have poor mental
and physical health as adults (Gupta, de Wit, & McKeown, 2007). Contrary to the report
of Gupta et al. (2007), Roy-Byrne, Joesch, Wang, and Kessler (2009) found that
socioeconomic status was not associated with physical and mental health services use
among 1,772 participants with mood and anxiety disorders. Age, gender, marital status
and race-ethnicity were significant predictors of mental health services use. Poor health
outcomes of individuals in low socio-economic status were more likely due to chronic
stress rather than due to the varied quality of treatment and/or services (Roy-Byrne et. al.,
2009).
A significant relationship between socio-economic status and health services use is
a consistent finding in many studies. Disparities related to demographic factors such as
age, gender, marital status, race, ethnicity, and education level are predictors of poverty
and warrant further research to mediate the effect of socio-economic status and health
services use in improving health outcomes.
Perceived Health Status. Perceived health status affects health behaviors and
health outcomes (Rahmqvist, 2001; Weigers & Drilea, 1999). Javier, Huffman, Mendoza,
and Wise (2010) examined usual source of care, health services use and perceived health
status of children with special needs (N=1,404). A lack of health care insurance and a
usual source care, no physician visits, fewer emergency room visits, and poor to fair
perceived health status were more likely to be reported among children from immigrant
families than the children from nonimmigrant families. Additionally, those children

22
belonging to undocumented families had decreased health care access and use as well as
poor health status. Language barriers, insurance policies, poverty status, ethnicity, and
citizenship status were possible reasons for lack of health care insurance and decrease use
of health care services (Javier et al., 2010). These findings support the relationship
between perceived health status and poor socio-economic conditions.
Rabin et al. (2009) reported perceived health status correlated with chronic disease
and increase morbidity and mortality in adults younger than 65 years. Age and race did
not explain a significant decline in perceived health status. However, education and
poverty reduction were identified as possible determinants of improved health outcomes.
Al-Windi (2005) reported that life satisfaction, the number of symptoms and depression
were predictors of perceived poor health among 470 multi-ethnic Swedish patients using
primary health care practices. Perceived health status had stronger correlation with mental
disorders than physical illnesses. People with mental disorders were more likely to have
poorer perceived health status than people with physical illness. Prospective studies on the
etiological background of perceived health and its association with demographic factors
and medical conditions are suggested routes for further investigations (Al-Windi, 2005).
Bethel, Foreman, and Burke (2011) examined the association of perceived health
status and chronic illness. Most of the respondents reported very good to excellent
perceived health status (52.3%). Perceived health status, number of chronic diseases and
disability status were the independent variables while the three natural disaster
preparedness plans were the dependent variables. Natural disaster (e.g., disease pandemic,
hurricanes, tornadoes, fire) preparedness plans included presence of four necessary
household items (e.g., water, radio, flashlight, and food), an emergency evacuation plan,
and a 3-day supply of medications. The researchers purported that U.S. respondents

23
(N=37,303) with fair/poor perceived health status and multiple chronic diseases were
more likely to have 3-day supply of medications but less likely to have the four necessary
household items and the emergency evacuation plan leading to greater vulnerability and
poorer health outcomes.
The association of perceived health status and health conditions was the main
focus of these studies. The impact of education level, health care practitioner’s
characteristics, and racial/ethnic disparities on perceived health status has not been
studied. Research examining the relationships of perceived health status, usual source of
care and health outcomes is limited. Prospective studies examining these relationships are
needed to identify strategies to improve health outcomes.
Health Attitudes. Consistent with the BMHSU model, health attitudes includes
opinions about health insurance coverage and the decisions to seek treatment. Health
attitudes about insurance coverage and medical treatment needs impact health services
use. Having adequate health insurance coverage assures an immediate and appropriate
health care delivery while having limited or no health insurance coverage leads to
discontinuation of health care services among U.S. non-institutionalized individuals with
Medicaid (N=6,247). A trusting patient-health care provider partnership and adequate
health insurance can contribute to establishing a usual source of care that supports
continuity of care and better patient outcomes. No insurance coverage may lead to
inpatient or emergency department use. Quality of health care delivery may be
compromised due to disruptions in health care insurance coverage, multiple variations of
health care providers and restrictions in the usual source of care (Benerjee, Ziegenfuss, &
Shah, 2010). Health insurance coverage is essential to access for care yet due to high costs
of health care many people with serious medical conditions have inadequate health

24
insurance coverage which limits their access to health care services use (Kass et al.,
2007). The strength of Benerjee et al. (2010) and Kass et al. (2007) studies is the
adequacy of sample size. Findings from these two studies demonstrated health insurance
coverage was associated with medical conditions. However, the focus on health attitudes
was not given an attention so little is known about the relationship of health attitudes to
health services use and health outcomes.
Cohen (2009) explored the attitudes toward health insurance and access to
healthcare among the 25 million U.S. civilian non-institutionalized adults age 18 and over
who participated in the Medical Expenditure Panel Survey (MEPS) 2006. According to
the U.S. Census Bureau (2010), in 2006 the U.S. population was estimated at
298,593,212. Hispanics were more likely to indicate they were healthy, had no need for
health insurance and health insurance was not worth the cost than White non-Hispanics
and Black non-Hispanics. Furthermore, males who had less than 12 years of education, a
low income, and were uninsured also reported being healthy, no need of health insurance
and health insurance was not worth the cost. These individuals were also less likely to
report ambulatory health care visits or inpatient stays (Cohen, 2009).
Negative attitudes about insurance coverage can have an impact on one’s health.
People without health insurance are less likely to use preventive health care services, thus
decreasing the likelihood of early recognition of health problems. As new regulations
regarding access to health care are implemented, studies are needed to determine if an
increase in access to health care improves attitudes about the health insurance and health
outcomes while decreasing health care disparities.

25
Enabling Resources
Usual Source of Care. Provider types such as the kind of facility and the site’s
health care providers are components of the construct of usual source of care in this study.
Self-reported sites for medical care are considered the usual source of care in this study.
Examples of medical sites are community clinics, emergency rooms, hospital clinics,
sheltered-based clinics and street outreach teams (Garibaldi et al., 2005). In a MEPS
study, usual source of care is assessed by asking the respondents the type of provider (e.g.
facility, person, person in the faculty) hospital/outpatient) and the specialty of the health
care practitioner (e.g., General/Family Practice, Internal Medicine,
Pediatrics, Obstetrics/Gynecology, Surgery, Chiropractor, Nurse, Nurse Practitioner,
Physician’s Assistant, Other Non-MD Provider, Cardiologist, Doctor of Osteopathy,
Endocrinologist, Gastroenterologist, Geriatrician, Nephrologist, Oncologist,
Pulmonologist, Rheumatologist, Psychiatrist/Psychologist, Neurologist, Alternative Care
Provider). Follow-up questions are asked regarding the characteristics of the health care
providers (Weinick, Zuvekas, & Drilea, 2006).
Disparities in health, usual source of care and health service use existed among
eligible male veterans (N=3227) in the Veterans Administration (VA) health care system.
The usual source of care included the emergency department, ambulatory care, and VA
and non-VA health facilities. Providers of health care included attending physicians,
resident physicians, nurse practitioners, or other health care providers. Blacks were likely
to have a usual source of care while Asian/Pacific Islanders were less likely to report their
usual provider of health care. Racial-ethnic disparities in usual source of care were
evident (Washington et al., 2005).

26
A study on the changes in usual source of care used a cross sectional data from the
1998-1999 Community Tracking Household Survey (N=48,720) conducted in a large
metropolitan area. Respondents without usual source of care (n=6,627) were more likely
to be White, young, male, unmarried, high school educated, and less likely to have private
insurance. A researcher suggested that future studies examine the influence of the
characteristics of the people with and without insurance coverage as insurance coverage
was not found to be different between individuals without usual source of care and those
with a change in usual source of care or continued usual source of care (Smith & Bartell,
2004).
Numerous studies have been conducted on usual source of care because of its
association with health related issues. However, the concept of usual source of care is
complex with no universally accepted description. The concept of usual source of care has
been used interchangeably with access to care and location of health care services
(Weinick et al., 2006).
Studies on usual source of care focused on variations among racial/ethnic groups.
Studies on usual source of care that identify the types of healthcare facilities and providers
that would best serve all racial/ethnic groups at all socio-economic levels were
recommended (Richardson & Norris, 2010). The samples in most studies on usual source
of care were Veterans homeless and older people, and people living in a large
geographical location. Research on the usual source of care using a sample of adults with
different health conditions particularly those with mental disorders and co-morbid mental
disorders and physical illness is warranted.
Personal/Family Resources
Insurance Status. Financial barriers such as unaffordable health insurance or
medical payments are major issues in mental health services use. Having no insurance

27
was associated with persons age 17-24 years, of minority racial-ethnic background,
unemployed, smoking, poverty, less than 12th grade education and poor health status
among young U.S. adults (N=9,004). After controlling for age, race, ethnicity,
employment, smoking, income, education and health status, lack of insurance
significantly increased likelihood of mortality. An alternative access to medical care (i.e.,
community health centers) for the individuals without insurance and advocating a
universal insurance coverage would be possible resolutions to decrease mortality and
improve health outcomes (Wilper et al., 2009). The presence of chronic and treatable
health conditions was not delineated as a cause of mortality in Wilper’s study. Insurance
and other demographic factors are known to be additional causes of mortality. Inclusion of
various health conditions would strengthen a study on the association of health insurance
with mortality.
Cheng (2005) studied the impact of welfare reform, health and insurance status on
welfare recipients’ (N=1,259, ages 18-64) health access. Hispanics were less likely to visit
a physician, use prescription medication or visit a dentist than non-Hispanics Whites.
Recipients of Temporary Assistance to Needy Families (TANF) perceived their health as
poor or fair but did use some type of health service. Use of health care services was
dependent on insurance. Non-Hispanics Whites were more likely to be insured than other
racial/ethnic groups. Race/ethnicity, health insurance status and welfare policies were
found to have significant effects on health care services use after controlling for prior
health care services, health status and demographic characteristics (Cheng, 2005).
Similarly, health insurance was found to be a predictor of patients (N=1414) use of
medical and chiropractic physicians among medical and chiropractic patients.
Chiropractors provided treatment for wide variety of medical conditions including

28
depression and other conditions that require prescription medications. Individuals with
public or private insurance were more likely to consult medical providers while those who
paid out of pocket were more likely to consult chiropractors (Legorreta et al., 2004;
Sharma, Haas, & Stano, 2003).
An ethical dilemma is often encountered when political actions involve welfare
reform and the regulation of health care and insurance coverage. Studies involving health
promotion and illness prevention in low income families could clarify political issues and
serve as a basis for meeting the health care needs of low income families. Attention to the
health care policies on financing mental health services and an increase of community
treatment centers may lessen the barrier in mental health service use (Herson & Snyder,
2011; Monheit, Cantor, DeLia, & Belloff, 2011; Woodward, Dwinell, & Arons, 1992).
Most studies on insurance explored the association of insurance coverage with the
type of medical provider. Studies that examine the relationships of health insurance, the
types of medical providers and health outcomes among individuals with mental disorders
are needed.
Health Care Practitioners’ Characteristics
Health care provider and client concordance in race/ethnicity has an impact on
individuals seeking health care service use for physical and/or mental problems. Allowing
time for patient-health care providers for conversation between patients and health care
providers facilitates attention not only to physical needs but also mental health needs. In
addition, having adequate training for health care providers on assessment, diagnosing and
treating patients with physical and mental disorders may alleviate barriers related to health
care providers’ attitudes related to the stigma of mental illness and improve health
outcomes (Hahm, Speliotics, & Bachman, 2008; Ndetan et al., 2010). The complexity of

29
mental disorders and factors inherent in the therapeutic rapport between individuals
seeking health care services and health care providers presents issues if providers are not
skilled on assessment, interview process and diagnosing of mental disorders and co-
morbidity (Desai, Rosenheck, & Craig, 2005; Flynn, Budd, & Modelski, 2008).
Cooper and Powe (2004) examined studies on health care provider-patient
racialethnic concordance (N=8). Racial and ethnic disparities were evident in few of the
studies they reviewed. Minority patients were treated by health care providers who were
of different racial and ethnic background. Studies on the impact of health care
providerpatient race-ethnic concordance to health services use and health outcomes were
limited.
The primary care physician’s office is a common place for studies on health care provider-
patient racial-ethnic concordance (Cooper & Powe, 2004).
Minorities are significantly more likely than Whites (n=3,488) to perceive biases
in medical treatment. They may feel that they would receive better medical care if they
belonged to a different race/ethnic group and would be treated with respect if they were of
a different race and ethnicity and could speak English well (N=6,299). Differences in
demographic factors, usual source of care, health status and concordance in
patientprovider characteristics have not been well explained. Future directions for
research include addressing these differences (Johnson, Saha, Arbelaez, Beach, & Cooper,
2004).
The client’s presentation of symptoms, the clinician’s degree of competence, and
organizational characteristics affect the diagnosis of mental disorders and substance
abuse. The client’s characteristics pertinent to their biophysiological status and the
severity of their disease are important aspects that influence the diagnosis of mental

30
disorders. Studies on diagnostic inaccuracy for substance abusing clients with mental
disorders have provided insights to the need of consistent diagnostic practices. Some
recommended diagnostic practices in providing treatment consistency for clients with
mental disorders and substance abuse include using comprehensive and detailed
evaluations on mental health and substance abuse history, performing structured
diagnostic clinical interviews and making accurate diagnostic differential (Kline &
Mehler, 2006).
Racial-ethnic disparities could be diminish by advocating for health care provider
diversity in the health care arena, instilling cultural competency among the health care
providers and augmenting funding resources on minority education. Future studies should
explore the effects of not only provider-patient racial-ethnic concordance; these studies
should include provider-patient gender concordance which has not been studied at all.
Community Resources
Adequacy of community resources is necessary to meet the treatment concerns
regarding the severity and chronicity of mental and physical illness. The choice of
treatment must be in accord to the client’s priorities and clients’ presentation of symptoms
(Flynn et al., 2008).
Usual Source of Care Location. The location of the usual source of care can
present a challenge. Potential barriers to clients’ accessibility to health care services
include a lack of financial resources, policies, laws, certification for mental health and
substance abuse, case management, integration of mental health and substance abuse care,
and scarcity of mental health care experts, community outreach programs, and public
transportation. The merging of funding sources, policies, services, education, training for
health care providers and utilization of peer recovery models may be the future

31
approaches to proper treatment of mental health disorders with co-morbidity issues and
reduce barriers to health care services use and accessibility (Ouimete et al., 2007;
Stefanacci & Podrazik, 2005).
Garibaldi et al. (2005) surveyed 531 homeless adults with self-reported a
comorbid mental disorder and physical illness to examine differences in accessing health
care services. Self-reported sites for medical care were considered the usual source of
care. Medical sites included community clinics, emergency rooms, hospital clinics,
shelter-based clinics and street outreach teams. Community clinics were used as the usual
source of care for medical care for both older (>50 years, n=457) and younger (<50 years,
n=74) adults. However older adults used more the shelter-based clinics and the streetbased
outreach programs than their younger counterparts. The researchers suggested augmenting
integration of mental health and physical services to improve health outcomes among
young and older homeless adults (Garibaldi et al., 2005).
Research comparing the use of different locations for usual source of care (e.g.,
emergency room vs. urgent care) and its effect on health behaviors and health outcomes is
much needed focus (Weinick, Burns, & Mahrotra, 2010). Future studies on differences of
community resources between individuals with mental disorders and individuals without
mental disorders are warranted. Additionally, the effects of the community resources on
health outcomes would be a direction of study to address health service use disparities.
Transportation Mode. Individuals with disabilities, especially for those with
mental disorders are less likely to have their own transportation. Shook (2005) assessed
the transportation barriers among 75 adult patients in a federally funded community health
center and found that lack of car ownership, longer distance travel, and reliance on public
transportation were significantly related to decreased health services use and poorer health

32
outcomes. Transportation barriers and lack of health insurance coverage were presented as
major issues in using the health services especially for people with chronic medical
condition (Shook, 2005).
In a study on older patients with bipolar disorder (N=58), researchers reported that
31% of the sample relied on public transportation (i.e. Veterans van) for medical
appointments and 22% had issues in accessing medical care. Disparities related to living
situations (i.e., being alone), transportation mode (i.e. relying on public transportation),
and health care services (i.e., accessing health care) increased their vulnerability.
Suggestions to improve health outcomes among people with a mental disorder and
physical illness included addressing transportation barriers, the implementation of medical
care models, the use of technology (i.e., telepsychiatry), and research on development of
treatment models (Kilbourne et al., 2008).
Convenience samples of older adults, Veterans, and homeless individuals were
used in most studies about community resources (i.e., usual source of care location and
transportation mode) and their relationship to health services use. The link between
community resources and health outcomes remained unclear and a topic for future
research. Furthermore, small sample sizes were a pattern in most studies on health
services use and access thus presenting a limitation. Future studies must address these
issues (i.e., diverse population, large sample size) to promote health and reduce health
disparities.
Health Behaviors
Health behaviors include health services use and health practice. In this study,
health behavior services use includes the total number of reported visits to outpatient and

33
office-based clinics for 2006. The health practice chosen for this study was the
participant’s smoking habit.
Health Services Use
A study on predictors of recent mental health service use reported interesting
findings on the importance of health care providers on individuals with medical
conditions. The strongest predictor of recent mental health service use in 240 adult
medical outpatients was the referral from health care provider for mental health services
(e.g., psychotropic medication, psychotherapy or combination of psychopharmacology
and psychotherapy). The trust and respect of patients for the health care providers who
referred them to mental health services has been implicated as one of the reasons for
adherence of medical patients to access mental health services referred by their provider.
Other predictors of recent mental health service use included the perceived need for
mental health services, prior use of mental health services, and the frequency of medical
appointments. A recommendation for future research includes exploring the relationship
of the characteristics of the providers (i.e. specific discipline) making mental health
referrals and patient compliance to accessing these services. Specific disciplines (e.g.,
physicians, nurse practitioners, and social workers) have been associated with patient
compliance to accessing recommended health care services (Ledoux, Barnett, Garcini, &
Baker, 2009).
Health care access and health care services utilization were examined in a study of
three generation Mexican Americans (N=4,382), non-Hispanic Blacks (N=4,138), and
non-Hispanic Whites (N=4,594). All three generations of Mexican Americans were more
likely to have low household income and use public health insurance coverage than
nonHispanic Whites. After controlling for socioeconomic factors and insurance status, the

34
first generation Mexican Americans had the highest rate of being uninsured and the lowest
level of health care access and health care services use. Cultural perspectives and
differences were attributed to health care services use. Language issues, lack of health
insurance, and difficulty with transportation and paying bills were identified as additional
barriers to health care services use (Burgos, Schetzina, Dixon, & Mendoza, 2005).
In the study of 363 homeless adults (predominantly young African American
males with a prison history, chronic alcohol dependence, no regular source of care and
currently receiving public benefits), researchers found that participants were more likely
to seek care for conditions that have less immediate impact but with more serious long
term consequences (e.g., high blood pressure; tuberculosis exposure) than those
conditions with more immediate impact (e.g., skin/leg/foot problems; vision impairment).
The use of health care was not associated with mental illness and substance abuse.
Satisfaction with care and perceived health status were positively associated with having a
regular source of care (community clinic or private physician). Homelessness was not a
barrier in obtaining health care services use as long as the homeless person believed that
the care was important (Gelberg et al., 2000).
In a cross sectional study of 1001 Hispanic respondents participating in the
Commonwealth Fund Minority Health Survey, the use of the health care system was
associated with having poor health status, a regular source of care, and health care
insurance coverage. The strongest determinants of number of visits within 12 months
were having a self-reported health problem; being female; having a large family size;
being foreign born; having health insurance; and having perceptions that better care is
received if race is non-Hispanic. People with health problems that interfered with their
work, school, housework and other activities were more likely to use emergency services.

35
Individuals with less than high school education and less than $25,000 annual household
income were less likely to use preventive care (Wagner & Guendelman, 2000).
Vega, Kolody, and Aguilar-Gaxiola (2001) compared the mental health services
use between foreign-born and U.S.-born Mexican Americans with psychiatric disorders
(N=507). Compared to the foreign born Mexican Americans, U.S.-born Mexican
Americans used more mental health specialists such as psychiatrists, psychologist, social
workers and other mental health providers. The foreign-born Mexican Americans used
more informal providers such as folk healers, and natural healers than U.S.-born Mexican
Americans. Significantly, U.S.-born Mexican Americans used one to three provider types
compared to foreign born Mexican Americans. Being female and knowing where to obtain
treatment were two statistically significant predisposing factors to seeking mental health
providers (Vega et al., 2001).
In a study of 1,772 National Comorbidity Survey Replication respondents with
anxiety and mood disorders, age, gender, marital status and race-ethnicity were strong
predictors of mental health services use. Education and income were weak predictors of
mental health services use. Most of the participants were age 30-44 (n=639, 34.5%),
females (n=1196, 64.8%), married (n=888, 48.7%), non-Hispanic Whites (n=1,272, 74%),
had insurance (n=1,551, 67%), 12 years of education (n=539, 31.5%), and high family
income (n=576, 32%). Non-Hispanic Whites were more likely had received mental health
services than Hispanic and non-Hispanic Blacks. The participants in lowaverage family
income and education lower than 12 years were less likely had mental health and general
medical health services but this result was found to be statistically significant. Variations
in the types of treatment settings, classification of psychotropic medications, and the

36
quality of health care services were possible reasons for mental health services use than
variations in education or socio-economic status (Adler &
Stewart, 2010; Roy-Byrne et al., 2009).
Although most studies have representative sample of Hispanics, an identified need
for more research exploring the ongoing issue of availability and accessibility of
diversified health care resources among the U.S. adult population lingers. Research on
differentiating the health services use between individuals with mental disorders and those
without mental disorders would facilitate understanding of health outcomes among
this population.
Health Practice
Smoking. Smoking is the most definite modifiable health risk factor that has a
negative association with health outcomes. Finney Rutten, Wanke, and Augustson (2005)
examined the association of health services use, usual source of care, perceived health
status, and smoking status (N=6,149). Non-smokers were more likely to have insurance
coverage; see a health care provider regularly; report very good to excellent perceived
health status and have fewer depressive symptoms. The researchers’ findings supported
that smoking has negative effects to usual source of care, health care services use and
perceived health status. Trosclair and Dube (2010) concurred that current smokers were
more likely to have mental disorders and nicotine dependence. Smoking cessation has
been suggested as an effective interventional strategy for mental health promotion
(Shimada, Lord, Yoshida, Kim, & Suzuki, 2007; Von Ah, Ebert, Ngamvitroj, Park, &
Kang, 2004).

37
Health Outcomes
In this study, health outcomes include physical health status and mental health
status. Population characteristics (predisposing factors and enabling resources) and health
behaviors (health services use and smoking) influence health outcomes.
Physical Health Status
Dawson, Grant, Chou, and Stinson (2007) examined the relationship of partner
alcohol problems and health outcomes among U.S. women age 18 and older (N=11,683).
The Short Form 12 items (SF-12) was used to measure physical health status. Women
with partner alcohol problems had a greater risk for multiple physical health problems and
poorer health status than those women without partner alcohol problems. One surprising
finding was that there were no differences in emergency department use or
hospitalizations among women with partner alcohol problems and women without partner
alcohol problems. Further exploration of the risk factors of women with partners who
have abusive behaviors was suggested to improve health outcomes of this population
(Dawson et al., 2007).
Everett, Mahler, Biblin, Ganghuli, and Mauer (2008) reported that people with
mental disorders have a higher mortality rate than the general public, however the cause
of deaths are usually preventable and manageable with positive health habits. Heart
diseases, cancer, lung conditions, stroke, accidents and diabetes are some of the physical
conditions known to cause premature deaths. Inadequate health care facilities, lack of
health insurance coverage, and incompetent health care providers were listed as some of
the barriers to positive health outcomes. Effective interventions for positive health
outcomes include smoking cessation, healthy lifestyles, and mental health policies
initiatives (Everett et al., 2008).

38
Studies showed that presence of physical illness, demographic factors (e.g., gender,
usual source of care, insurance status), and health care practitioner’s characteristics were
predictors of physical health status. Exploration on the association of other socio-
demographic factors (e.g., health attitudes, perceived health status, health behaviors,
usual source of care) with physical health status has not been well researched. Further
investigation of the relationship of socio-demographic variables such as health attitudes,
perceived health status, health behaviors, usual source of care and various types of
physical health conditions would provide a better understanding of physical health status.
Mental Health Status
Timko and colleagues (2006) focused on health outcomes, health care utilization
and costs among 230 Veterans. Veterans with mental disorders and substance abuse living
in the community residential facilities were found to have better mental health outcomes
(i.e. less severe psychiatric symptoms and substance use; less health care cost and
utilization of services) compared to those in the hospital acute care facilities. Patients in
the hospital acute care facilities had more outpatient mental health follow-up visits
(mean=96.42, SD=88.59) and more costly mental health follow-up visits than the patients
in the community residential facilities (Timko, Chen, Sempel, & Barnett, 2006). In
addition, veterans with more severe mental disorders and substance abuse and in high
service intensity programs had higher mental health care use in both inpatient and
outpatient treatment settings than those in a less severe and low service intensity group
(Timko et al., 2006; Chen, Barnett, Sempel, & Timko, 2006).
In a randomized controlled trial (N=152), patients with severe and persistent
mental and substance use disorders were found to have a significant increased use of
outpatient management contacts and medication visits. Bipolar patients with substance use

39
disorders had better mental health outcomes than those with schizophrenia or
schizoaffective with substance use disorders (Xie, McHugo, Helmstetter, & Drake, 2005).
The integration of physical and mental health services is a recommended strategy to
provide holistic care and improve both physical and mental health status. Future studies
must include the effects of integrated health care service to health outcomes
(Anderson et al., 2010).
A significant association of health services use and mental health status is evident.
Studies indicate that the severity of having a mental health condition affects health
services use and mental health status among individuals with mental disorders. However,
studies that examine the relationships of health conditions, usual source of care, insurance
status, health care practitioner’s characteristics, health attitudes, perceived health status,
health behaviors with mental health status are limited.
Summary
Most studies reviewed used varied sample size (e.g., 8-531) from convenience
samples to large samples (e.g., <1,000 -25 million) from national surveys (e.g., Medical
Expenditure Panel Survey, National Comorbidity Survey Replication). Studies with small
sample size were valuable in highlighting the needs of specific population (e.g., children,
older adults, homeless people, Veterans). Studies from national surveys with large sample
size were useful in pointing out the usual source of care and health conditions of
individuals with mental health conditions across the nation.
Most studies on mental health were descriptive and often suggested the need for
interventions. However, interventional research was limited. The literature identified a gap
on the relationships of health conditions, socio-demographic factors, health attitudes,
perceived health status, usual source of care, health services use, smoking, and health

40
outcomes. Most studies examined the relationships of a few of these constructs but there
was no study that examined the relationships of all of these constructs (i.e., health
conditions, socio-demographic factors, health attitudes, perceived health status, usual
source of care, community resources, insurance status, health services use, smoking,
health outcomes). Additionally, there was no study that examined the influence of these
relationships to health behaviors and health outcomes and used a theoretical model (i.e.,
Behavioral Model of Health Services Use). There were limited studies on the differences
of usual source of care, physical health status and mental health status between
individuals with mental disorders and those without mental disorders. A study with a
focus on individuals with self reported mental disorders and their perceived status, usual
source of care, and health outcomes adds to the limited number of reports on these aspects
of need.

CHAPTER III
Methodology
This chapter describes the research design used in this study. Assumptions about
the data are presented. Data sources, sample, measurements, and analytical approaches
are discussed.
Research Design and Data Sources
This study is a secondary analysis of existing data collected from the national
public data base Medical Expenditure Panel Survey (MEPS) of 2006. The MEPS was
initiated in 1996 by the Agency for Healthcare Research and Quality (AHRQ) to collect
data annually on financing and utilization of medical care by the general population in the
United States. The MEPS provides the most complete national database on health
conditions, access to care, insurance status, health services use, and health status of the
American populace. The MEPS consists of two main components, the household
component and insurance component. The Household Component (HC) contained data
from a sample of individuals, families and their medical providers. The Insurance
Component (IC) included data from employers about their health insurance. MEPS
HC104 contained a list of medical conditions in 2006 (MEPS Survey Background, 2010).
Health conditions were selected from MEPS HC-104 2006. Survey questionnaires related
to specific topics such as access to care, health insurance, health status and hospital visits

42
43
were used in MEPS HC-105. MEPS HC-104 and the 2006 Consolidated Data File of
Household Component (HC-105) were used in this study.
The National Health Interview Survey, conducted by the National Center for
Health Statistics, was used in a sampling frame that consisted of a U.S. civilian
noninstitutionalized population for MEPS. Data were collected using computer-assisted
personal interviewing (CAPI) technology in a 2.5 year period. Interviews were
administered in person and ranged from one to four hours with an average of 90 minutes
depending on the number of persons per household and their health care use. An
overlapping panel design was used by MEPS in the data collection. Each Panel consisted
of five rounds of interviews over the 2.5-year period of data collection starting from
January 1st to December of 31st. Panel 10 and Panel 11 were used in the 2006 data
collection period. The two Panels were indicated by letters X and Y. Panel 10 was
denoted by X and Panel 11 was denoted by Y. Both Panel 10 and Panel 11 have
corresponding rounds of interviews. Panel 10 consisted of Rounds 3, 4 and 5 and Panel
11 consisted of Rounds 1, 2 and 3. The number after each variable name represented the
rounds when the data were collected (MEPS-HC Sample Design and Collection Process,
2010). Panel 10 (X) and Round 4 and Round 2 (42) were used in this study to have
consistency of the variables collected in the same time period.
Data collected in MEPS 2006 was used in this study because this time period had
the largest sample size and reporting units as compared to the data collected between
2004 and 2008. All of the variables used in this study were available during this data
collection. The structure of the Behavioral Model of Health Service Use (BMHSU) was
used to present the constructs, variables and their operational definitions and the specific

43
data source; see Table 3.1. See Appendix A for the detailed description of variables
categorized according to the concepts of the modified version of BMHSU.
Table 3-1
BMHSU Constructs, Variable Operational Definitions and Specific Source for MEPS
Data*
BMHSU Variable Specific
Constructs Operational Definition Data Source
Population Characteristics
Predisposing Factors
Health Conditions Mental Disorder MEPS HC-104
Schizophrenia CCCODEX 659
Mood disorder CCCODEX 657
Physical Illness MEPS HC104
Hypertension CCCODEX 098
Hyperlipidemia CCCODEX 053
Co-morbid Mental Disorder MEPSHC-104
And Physical Illness
CCCOODEX
Demographic Age (18-24, 25-44 and MEPS HC-105-RE
Factors 45-65 years old)
AGE42X
Gender (Male or MEPS HC-105-RE
Female) SEX
Marital Status MEPS HC-105-RE
(Married, Widowed, MARRY42X
44
Divorced, Separated,
Never Married, and
Under 16-inapplicable.
Race (Whites, Black, MEPS HC-105-RE
American Indian, Asian.
Native Hawaiian or Pacific
RACEX
Islander, Multiple Races)
(Table 3-1 Continues)
(Table 3-1 Continued)
BMHSU Variable Specific
Constructs Operational Definition Data Source
Ethnicity (Hispanic, MEPS HC-105-RE
Not Hispanic) HISPANX
Education (No Degree, GED, MEPS HC-105-RE
High School Diploma,
Bachelor’s degree, Master’s
Degree, Doctorate Degree,
Other degree and Under
16-inapplicable
HIDEG
Socio-Economic Poverty Status (Poor, MEPS HC-105
Status Near-poor, Low income, Constructed
Middle income, High POVCAT06
Income)
Health Attitudes Health Attitudes toward MEPS HC-105-SAQ
health insurance and (HEALTH
decision factor to purchase ATTITUDES
health insurance or to use health (Merged
services (5 points Likert scale ADOVER42
Disagree Strongly, Disagree ADINSA42
Somewhat, Uncertain, Agree ADINSB42
45
Somewhat, Agree Strongly) ADRISK42)
Perceived Health Perceived Health Status MEPS HC-105-CE
Status Rate of General Health RTHLTH42
(Excellent, Very Good,
Good, Fair, Poor, Inapplicable)
Perceived Mental Status MEPS HC-105-CE
Rate of Mental Health MNHLTH42
(Excellent, Very Good,
Enabling Resources
Good, Fair, Poor, Inapplicable)
Usual Source of Care Provider Type MEPS HC-105-PV
(Facility, Person,
Person in Facility Provider
PROVTY42
(Table 3-1 Continues)
(Table 3-1 Continued)
BMHSU Variable Specific
Constructs Operational Definition Data Source
Health Care Practitioners’ Health Care Practitioner’s HC-105-AC
Characteristics Gender (Male, Female, GENDRP-42
Unknown)
Health Care Practitioner’s Race HC-105-AC
(Hispanic HSPLAP-42
White, WHITPR-42
Black/African American, BLCKPR-42
Asian ASIANP-42
Indian/Native American/Alaska NATAMP-42
Other Pacific Islander, PACISP-42
Some other race) OTHRCP-42

46
Health Care Practitioner’s MEPS HC-105-AC
Ethnicity (Hispanic-Yes/No) HSPLAP42
Personal/ Insurance status MEPS HC-105
Family Resources Presence of health insurance Constructed
Coverage (Any Private,
Public only; Uninsured)
INSCOV06
Community Resources Usual Source of Care Location MEPS HC-105
(Office, Hospital Clinics (not ER), Constructed
Hospital ER LOCATN42
Transportation Mode (Self- MEPS HC105-AC
Driven, Somebody Driving, GOTOUS42
Use of Public Transportation,
Walking)
Health Behaviors
Health Services Use Total Number of Office-Based MEPS HC-105 Clinic
Visits for 2006 Health Services
OBTOTV06
(Table 3-1 Continues)
(Table 3-1 Continued)
BMHSU Variable Specific
Constructs Operational Definition Data Source
Total Number of Outpatient-Based MEPS HC-105
Clinic Visits for 2006 Health Services
OPTOTV06
Health Practice Smoking (Currently Smoke- MEPS HC-105-SAQ
Yes or No)
ADSMOK42
(Table 3-1 Continues)
Health Outcomes Physical Health Status MEPS HC-105-SAQ
SF-12 (PCS42)

47
(Physical Component
Summary)
Mental Health Status MEPS HC-105-SAQ
SF-12 (MCS42)
(Mental Component
Summary)
________________________________________________________________________
* MEPS 2006 HC-105 Consolidated Data
The medical conditions were recorded and coded using International
Classification of Diseases, Ninth Revision, Clinical Modification (ICD-9-CM). ICD-9-
CM was the official system for assigning codes to diseases or diagnoses in the United
States (Centers for Disease Control and Prevention, 2010). ICD-9-CM condition codes
have been aggregated into similar meaningful categories known as Clinical Classification
Codes (CCC) (MEPS Medical Condition, 2010). The medical condition of 2006 HC-104
CCCODEX data file contained clinical diagnostic codes and was used to identify subjects
for this study. The numbers after the data source on CCCODEX represent the ICD-9-CM
or the codes to the disease or diagnoses chosen for the study.
MEPS HC-105 2006 full year consolidated data file was used as the main data
source of the study variables. Subjects were selected for this study with the use of a
unique identifiable variable (DUPERSID). DUPERSID contained the person’s dwelling
unit identification and person’s number (N=34,145). The subjects selected from the
medical condition of 2006 HC-104 were matched and merged with the subjects in MEPS
HC-105 2006 full year consolidated data file (N=622). The main variables and associated
variables were selected and presented according to the category of the concepts of the
modified BMHSU. See Appendix A for detailed description of variables and coding.

48
Sample
Sample criteria were set according to the category of the health conditions. The
health conditions were categorized according to the disorder/illness group. The first
category consisted of the mental disorder (MD) group. The mental disorder group
consisted of individuals with schizophrenias, psychoses, and mood disorders but without
cancer, dementia or emergent conditions or surgery or fractures (n=114). The second
category consisted of the physical illness (PI) group. The physical illness group consisted
of individuals with hypertension (high blood pressure) and hyperlipidemia (high
cholesterol, high levels of lipids) but without any other physical conditions (n=469). The
third category consisted of the co-morbid (CM) mental disorder and physical illness
group. The co-morbid group consisted of individuals with both a mental disorder and a
physical illness (n=39). Mental disorders and physical illnesses were determined
according to ICD-9-CM. The health condition categories and total number of subjects are
summarized in Table 3.2.
Table 3-2
Health Condition Categories
Health Condition Category n %
Mental Disorder (MD) 114 18
Physical Illness (PI) 469 76
Co-morbid Mental Disorder
and Physical Illness (CM)
39 6
No individual identifiers were used in the study. The inclusion criterion was being
a U.S. civilian non-institutionalized adult aged 18 and above but less than 67 years
regardless of gender, educational status, marital status, and race-ethnic background. To be

49
included in the 2006 MEPS study, the participant had to be at least 65 years old; some
participants were 65 years at the start of the study but at the time of their enrollment into
the study, they were 66 years of age. The individuals with mental disorders have
selfreported schizophrenia, psychoses, and mood disorders. These mental disorders were
selected due to their chronicity and severity (Parabiaghi, Bonetto, Rugerri, Lasalvia, &
Leese, 2006). The individuals without mental disorders have self-reported physical
illnesses such as hypertension (high blood pressure) and hyperlipidemia (high
cholesterol). These selected physical illnesses are costly, chronic, life threatening
conditions but are treatable and are not considered terminal illnesses (MEPS, 2010).
Criteria for exclusion were a) age 17 and below; b) age 67 and above; c)
psychiatric diagnoses such as those commonly diagnosed in children (i.e., oppositional
defiant disorder and conduct disorder, developmental disorders); d) vague psychiatric
diagnoses (i.e., miscellaneous mental disorders, suicide and intentional self-infliction,
history of mental health); and e) other psychiatric diagnoses categorized as Diagnostic
Statistical Manual Fourth Edition Text Revision (DSM IV-TR) Axis II diagnoses (i.e.,
personality disorders and mental retardation).
Psychiatric diagnoses commonly seen in children ages 17 and below were
excluded in the study because of the differences in the assessment, diagnosis, treatment,
and mental health services for individuals age 17 and younger as compared to individuals
age 18 and older (Calton & Arcelus, 2003; Simonoff et al., 2004). Ages 66 and above
were excluded in the study because of the differences in the assessment, diagnosis,
treatment and biopsychosocial needs of individuals age 65 and older as compared to
individuals below 65 years old (Cummings & Cassie, 2008). Vague psychiatric diagnoses
and DSM IV-TR Axis II diagnoses were excluded because these were not considered

50
severe mental disorders. Additionally, other long term, life threatening medical/physical
illnesses such as cancer, diabetes, emphysema and stroke were excluded because of the
known treatment complexity and illness severity associated with these diseases (MEPS,
2010).
According to Munro (2001), the power of a MANOVA study is difficult to
determine because of the number of variables that needed to be estimated. In order to
maintain a given level of power, an increase number of dependent variables require an
increase in sample size. However, a minimum of 10 subjects per variable is needed to
conduct a regression analysis. Using this estimation and basing the sample size
determination on the 25 variables for Aim 1 Research Question 4 (A1R4), the minimum
sample size for the study is 250 participants. For comparison, the sample size was
estimated for an ANOVA analysis for Aim 2 Research Question 2 (A2R2), is there a
significant difference in physical health status between individuals with self-reported
mental disorders and individuals without mental disorders. Based on A2R2, a minimum
of 50 subjects was projected for 3 independent variables and 2 dependent variables. The
sample size of this study was 622 participants, far exceeding the minimum requirements
for the sample size estimations presented above. Of interest for the national study,
Ferguson (2009) notes that small effect sizes are common in social sciences research
(Ferguson, 2009; Rosnow & Rosenthal, 2003). The effect size of .15 was obtained for
this study with alpha=.05 and power of 0.8.
Measurements
MEPS has established survey questionnaires specific to the topic of this research
study. The established survey questionnaires included in the study were the access of care

51
(AC), health insurance (HX), health status (HE), medical provider visits (MV), medical
conditions (MD), and satisfaction with their health plan (SP) (MEPS, 2010). See
Appendix B for the definitions of terms.
Periodically, MEPS administers a paper questionnaire that includes the adult
SelfAdministered Questionnaire (SAQ). The SAQ contains questions from several
measurements such as The Consumer Assessment of Health Plans (CAHPS), the
ShortForm-12 items (SF-12), the Kessler Index (K6) and the Patient Health
Questionnaire (PHQ-2). Two supplement questionnaires collected by MEPS interviewers
but not used in this study were The 2000 Parent Administered Questionnaire (PAQ) and A
Survey about your Diabetes Care (MEPS, 2010). K6 and PHQ-2 were not used as a data
source
in this study.
The question on smoking (ADSMOK42) was taken from one of the
measurements of CAHPS. Participants were asked if they were currently smoking with
responses of yes or no. CAHPS is designed to measure quality of care from the
respondent’s perspectives (MEPS, 2008).
Health Attitudes includes opinions on health insurance and decision factors in
purchasing health insurance and use of health services. The health attitude variable was
derived from the Self-Administered Questionnaire (SAQ) data on ADINSA42,
ADINSB42, ADRISK42 and ADOVER42. ADINSA42 is defined as “healthy enough”
and “do not need health insurance”. ADINSB42 is defined as “health insurance is not
worth the money it costs”. ADRISK42 is defined as “more likely to take risks than the
average person”. ADOVER42 is defined as “can overcome illness without medical help”.
Initially two variables were merged together (ADINSA42 and ADINSB42) and
(ADINSB42 and ADRISK42) based on their relevance to concepts of health insurance

52
and health services use. The reliability of the two variables resulted to .405, however,
when all four variables (ADINSA42, ADINSB42, ADINSB42 and ADRISK42) were
merged the reliability increased to .611. The four variables (ADINSA42, ADINSB42,
ADRISK42 and ADOVER42) were renamed health attitudes (HEALTHATTITUDES).
According to George and Mallery (2003), the reliability of .611 with only four items is
acceptable. A 5-point Likert scale was used for each health attitude with the higher score
indicating an agreement to the item. For example a score of 5 on the item regarding the
need for health insurance would indicate that the respondent felt that health insurance is
not important. The higher the score of health attitudes meant that the insurance was not
needed and not worth the cost. The range of scores for the four items is 0 to 20 (MEPS,
2008).
The variables on health outcomes of this study are the Physical Component
Summary (PCS) of the Short Form-12 Items version 2-Imputed (SF-12v2) and the Mental
Health Component (MCS) of the SF-12v2 Imputed. The Short Form-12 Items (SF-12) is
a widely used measurement for health status. The SF-12 contains twelve questions
relevant to the limitations of activities of daily living or ability to do physical activities;
the frequency of feeling calm, downhearted, and energized; and overall health. The SF-12
contains two main components, the Physical Component Summary (PCS) and the Mental
Component Summary (MCS). The SF-12 has also been preliminary tested for reliability
and validity with the 36-item Short Form Health Survey (SF-36) with 2,333 U.S.
Americans. A test-retest correlation of 0.89 was reported for the 12-item PCS and 0.76
for the 12-item MCS. In validity tests, the relative validity estimate ranged from 0.43 to
0.93 (median=0.67) for the 12- item PCS and from 0.60 to 1.07 (median=0.97) for the
12-item MCS (Ware, Kosinski, & Keller, 1996). The reliability and validity of SF-12

53
have been established based on data from 145 homeless people with Cronbach’s Alpha of
0.82 for physical health and 0.79 for mental health with comparison estimates from the
general population of 0.78 for physical health and 0.73 for mental health (Larson, 2002).
In addition, Fleishman (2010) found correlations among the PSC-12 and MCS-12 scales
were high (>/=0.84) among 53,399 U.S. respondents. The alpha coefficient for this study
is .997, suggesting that the 12 items of SF-12 have high internal consistency.
Data Assumptions
This study has two basic assumptions. First, the Medical Expenditure Panel
Survey (MEPS) was administered accurately. Professional coders used the International
Classification of Diseases Ninth Revision (ICD-9-CM) for coding the medical conditions
(MEPS Medical Condition, 2010). It is assumed that the information on medical
conditions coded in the data base has been entered correctly. Second, it is assumed that
all participants answered the questions to the best of their ability. Data were taken from a
self-report survey completed by respondents (N=622). It is assumed that these
respondents gave honest responses related to their health conditions, demographic
information, socio-economic structure, health attitudes, perceived health status, usual
source of care, health services use, health practice, and physical health status and mental
health status.
Data Analysis Procedures
The Statistical Package for Social Sciences (SPSS) Program version 18.0 was
used in analyzing the data. Descriptive analyses were first carried out to examine the
characteristics of the subjects and group comparisons between individuals with
selfreported mental disorders and those without mental disorders. An explorative

54
descriptive analysis was used to describe the relationship of population characteristics
(predisposing factors and enabling resources), health behaviors (health services use and
health practice) and health outcomes (physical health status and mental health status) of
individuals with self-reported mental disorders (MD), physical illnesses (PI) and a co-
morbid mental disorder and physical illness (CM). Differences in usual source of care,
physical health status and mental health status between individuals with self-reported
mental disorders and individuals without mental disorders were also examined using
descriptive analyses.
For Aim1Research Question 1 (A1R1) and Aim 1 Research Question 3 (A1R3) a
general linear model or multivariate analysis of variance (MANOVA) was used to
analyze the relationships of population characteristics (predisposing factors and enabling
resources), health behaviors, and health outcomes. For Aim 1Research Question 2
(A1R2) and Aim 1 Research Question 4 (A1R4), a multivariate analysis of covariance
(MANCOVA) was used to analyze the relationships of population characteristics
(predisposing factors and enabling resources), health behaviors, and health outcomes. For
A1R1, population characteristics (predisposing factors and enabling resources) were the
independent variables and health behaviors were the dependent variables. For A1R2,
predisposing factors were the independent variables, enabling resources were covariates,
and health behaviors were the dependent variables. For A1R3, population characteristics
(predisposing factors and enabling resources) and health behaviors were the independent
variables and health outcomes were the dependent variables. For A1R4, predisposing
factors and health behaviors were the independent variables, enabling resources were
covariates and health outcomes were the dependent variables.

55
For Aim 2 Research Question 1 (A1R1), a Kruskal-Wallis one-way analysis of
variance was used to analyze the differences in the usual source of care between
individuals with self-reported mental disorders and individuals without mental disorders.
Health conditions, [mental disorders (MD), physical illness (PI), and co-morbid mental
disorder and physical illness (CM)] were the independent variables and usual source of
care was the dependent variable. For Aim 2 Research Question 2 (A2R2) and Aim 2
Research Question 3 (A2R3), a univariate analysis of variance (ANOVA) was used to
analyze the differences in the physical health status and mental health status between
individuals with self-reported mental disorders and individuals without mental disorders.
The health conditions (MD, PI and CM) were the independent variables for A2R1, A2R2
and A2R3. The dependent variable for A2R1 was usual source of care, for A2R2 physical
health status and for A2R3 mental health status.
In summary, a general linear model or multivariate analysis of variance and
multivariate analysis of covariance were used to analyze the relationships of population
characteristics, health behaviors and health outcomes. A univariate analysis of variance
was used to analyze the differences in the usual source of care, physical health status and
mental health status between individuals with self-reported mental disorders and
individuals without mental disorders. A significance level of p<.05 was used for analysis.
All results with p=<.05 were considered statistically significant.
Summary
This study was a secondary analysis of existing data collected from the national
public data base Medical Expenditure Panel Survey (MEPS) of 2006. The MEPS
Household Component (HC-105) 2006 full year consolidated data file was the data
source of the study variables. U.S. civilian non-institutionalized adults ages 18 years and

56
above but less than 65 years old regardless of gender, educational status, marital status,
and race-ethnic background (N=622) were included in this study. The sample was
selected based on the following health conditions: mental disorders (MD), physical
illnesses (PI), and co-morbid mental disorders and physical illnesses (CM).
The two assumptions related to the study were presented. A general linear model
or multivariate analysis of variance was used to analyze A1R1 and A1R3 while a
multivariate analysis of covariance was used to analyze A1R2 and A1R4. A univariate
analysis of variance was used to analyze A2R1, A2R2 and A2R3. Results with a
significance level of p<.05 were considered as statistically significant.

CHAPTER IV
Results
This chapter contains the results of the data analyses. Sample characteristics are
described. Descriptive statistics for major study variables such as population
characteristics (predisposing factors and enabling resources), health behaviors (health
services use and health practice) and health outcomes (physical health status and mental
health status) are discussed. Discussion of the results and data analyses are organized
according to the two specific aims and their corresponding research questions.
Sample Characteristics
Descriptive statistics that included means (M), standard deviation (SD), ranges
and frequencies were used to analyze the demographic data. The sample (N=622) was
categorized according to the three health conditions: a mental disorder (n=114, 18%), a
physical illness (n=469, 76%); and a co-morbid mental disorder and physical illness
(n=39, 6%). The ages ranged from 18 to 66 years old. Age was based on the date of birth
upon participation of MEPS (January 1st to December 31st2006). The participants must be
65 years at the start of MEPS 2006 study. The mean age of individuals with a mental
disorder (MD) was 37 (SD=11) years. The mean age of individuals with a physical illness
(PI) was 48 (SD=10) years. The mean age of individuals with a co-morbid mental
disorder and physical illness (CM) was 45 (SD=13) years. An ANOVA was used to

58
59
identify age differences between the three health conditions. There were statistically
significant differences in age between the three health conditions, F (2, 619) =46.22,
p=.000). Individuals with MD were significantly younger than the individuals with CM
(p=.001) and individuals with PI (p=.000). Individuals with PI were significantly older
than the individuals with MD. Individuals with PI were older than the individuals with
CM but was non-significant difference (p=.200).
A Chi square analysis was used to identify differences in demographic factors
between the three groups (MD, PI, and CM). There were statistically significant
differences among gender, X2 (2, N=622) = 6.667, p <.01; race, X2 (10, N=622) = 42.88, p
<.01; ethnicity, X2 (8, N=622)=37.18, p <.01; marital status, X2 (10, N=622)=113.44, p
<.01; and poverty status, X2 (8, N=622)=97.93, p <.01. No significant difference on
education between the three health conditions, X2 (16, N=622) = 17.8, p=.336.
The majority of the sample was male (n=342; 55%), White (n=416; 67%),
nonHispanic (n=292; 47%), and married (n=395; 64%), had a high school diploma
(n=302, 49%) and reported a middle to high income (n=373, 60%). Males were
predominant in both the PI (n=262, 59%) and CM (n=27, 69%) groups while females
were predominant in the on MD group (n=61, 53%). The majority of the individuals
reported a PI; these individuals were likely to be White (n=306, 74%) and non Hispanic
(n=193, 66%). Noteworthy, all Asians (n=34) in the study self-identified their health
conditions as PI; no
Asians reported a MD or a CM.
The majority of the individuals with PI (n=344, 73%) and CM (n=13, 33%)
reported being married. The majority of the individuals with MD were never married
59
(n=42, 36%). Those who identified themselves as widowed in the study (n=17) were
individuals with a PI and 50% of the widowed were Asians.
According to poverty status, individuals with MD and CM reported a lower
income while individuals with PI were likely to have a high income. The majority of the
individuals with PI either identified themselves as having no degree (n=108, 23%) or a
high school diploma (n=219, 47%). Demographic characteristics are presented in Table
4.1.
Table 4-1
Demographic Characteristics
Demographic Mental Disorder (MD) Physical Illness (PI) Co-Morbid (CM)
Characteristics n=114 (18%) n=469 (76%) n=39 (6%)
n(%) n (%) n (%)
Gender
Male 53 (15%) 262 (77%) 27 (8%)
Female
Race
61 (22%) 207 (74%) 12 (4%)
White 80 (19%) 306 (74%) 30 (7%)
Black 25 (16%) 125 (80%) 6 (4%)
American Indian 1 (33%) 2 (67%) 0 (0%)
Asian 0 (0%) 34 (100%) 0 (0%)
Pacific Islander 1 (50%) 1 (50%) 0 (0%)
Multiple Races
Ethnicity
7 (64%) 1 (9%) 3 (27%)
Black Not Hispanic 23 (15%) 125 (81%) 6 (4%)
Asian Not Hispanic 0 (0%) 33 (100%) 0 (0%)
Not Hispanic 70 (24%) 193 (66%) 29 (10%)
Non-Mexican Hispanic 7 (15%) 36 (76%) 4 (9%)
Mexican-Hispanic 14 (15%)
82 (85%) 0 (0%)
(Table 4-1 Continues)
60
(Table 4-1 Continued)
Demographic Mental Disorder (MD) Physical Illness (PI) Co-Morbid (CM)
Characteristics n=114 (18%) n=469 (76%) n=39 (6%)
n(%) n (%) n (%)
Marital Status
Married 38 (10%) 344 (87%) 13 (3%)
Widowed 0 (0%) 17 (100%) 0 (0%)
Divorced 24 (27%) 54 (60%) 12 (13%)
Separated 10 (53%) 8 (42%) 1 (5%)
Never Married 42 (42%) 45 (45%) 13 (13%)
Education
No Degree 26 (19%) 108 (77%) 6 (4%)
GED 5 (24%) 12 (57%) 4 (19%)
High School Diploma 61 (20%) 219 (73%) 22 (7%)
Bachelor’s Degree 10 (12%) 72 (84%) 4 (4%)
Master’s Degree 5 (17%) 24 (83%) 0 (0%)
Doctorate Degree 1 (11%) 8 (89%) 0 (0%)
Unspecified 2 (25%) 6 (75%) 0 (0%)
Other Degree 4 (15%) 20 (74%) 3 (11%)
Socio-Economic Status (Poverty Status)
Poor 47 (44%) 27 (44%) 12 (12%)
Near Poor 8 (21%) 23 (60%) 7 (19%)
Low Income 23 (22%) 74 (70%) 8 (8%)
Middle Income 22 (12%) 161 (86%) 4 (2%)
High Income 14 (8%) 164 (88%) 8 (4%)
Descriptive Statistics for Major Study Variables
The major study variables included population characteristics (predisposing
factors {health conditions, demographic factors, poverty status, health attitudes,
perceived mental health status} and enabling resources {usual source of care, health care
practitioners’ characteristics, personal/family resources and community resources});

61
health behaviors (health services use and health practice) and health outcomes (physical
and mental health status). Each of the major study variables are presented and described
according to the Modified Behavioral Model of Health Service Use.
Population Characteristics
Predisposing Factors
Predisposing factors include health conditions, demographic factors, poverty
status, health attitudes, and perceived health status. Health conditions, demographic
factors and poverty status were discussed previously. Descriptive statistics for health
attitudes and perceived health status (perceived health status and perceived mental health
status) were obtained and categorized according to participant’s self-identified health
conditions, [mental disorder (MD), physical illness (PI) and co-morbid mental disorder
and physical illness (CM)]. Over 80% of the participants (n=533, 84%) rated their health
attitudes. Health attitudes score ranged from 4.00 to 20.00 (M=7.95, SD=3.35). The lower
scores (4.00) reflect disagreement with the item on the scale while higher scores indicate
agreement with the item on the scale. Participants’ low scores indicated that health
insurance was worth the cost, that they were not likely to take risks and that they could
not overcome illness without help. An ANOVA was used to identify health attitudes
differences between the health conditions. There were no statistically significant
differences in health attitudes between the individuals with MD, PI and CM, F (2, 4.2)
=.38, p=.69). Chi square analyses identified significant differences in perceived health
status, X2 (10, N=622) =81.56, p <.01 and perceived mental health status, X2 (10, N=622)
= 208.77, p <.01 between the three health condition groups. The majority of the
participants rated their perceived health status (n=519, 83%) and perceived mental health
status (n=530, 85%) from “good” to “excellent”. Most of the individuals with MD rated
62
their perceived health status (n=46, 40%) and perceived mental health status (n=35, 31%)
as “good”. Most of the individuals with PI rated their perceived health status (n=177,
38%) and perceived mental health status (n=159, 34%) as “very good”. Most of the
individuals with CM rated their perceived health status as fair (n=13, 33%) while their
perceived mental health status was reported as “good” (n=14, 36%). Detailed descriptive
statistics for perceived health status) are described in Table 4.2.
Table 4-2
Descriptive Statistics of Perceived Health Status
________________________________________________________________________
Perceived Health Status Health Condition
________________________________________________
Variables MD (n=114, 18%) PI (n=469, 76%) CM (n=39, 6%) n (%)
n (%) n (%)
Perceived Health Status
Excellent 14 (14%) 83 (85%) 1 (1%)
Very Good 23 (11%) 177 (85%) 9 (4%)
Good 46 (22%) 156 (73%) 10 (5%)
Fair 24 (30%) 43 (54%) 13 (16%)
Poor 7 (44%) 3 (19%) 6 (37%)
Inapplicable*
Perceived Mental Health Status
0 (0%) 7 (100%) 0 (0%)
Excellent 11 (7%) 148 (92%) 1 (1%)
Very Good 20 (11%) 159 (87%) 3 (2%)
Good 35 (19%) 139 (74%) 14 (7%)
Fair 32 (54%) 16 (27%) 11(19%)
Poor 16 (62%) 0 (0%) 10 (38%)
Inapplicable* 0 (0%) 7 (100%) 0 (0%)
________________________________________________________________________
*Inapplicable: Question skipped by participants.

63
Enabling Resources
Descriptive statistics for enabling resources were obtained and categorized
according to participant’s self-identified health conditions (MD, PI and CM). Enabling
resources included usual source of care (provider type), personal and family resources
(insurance status), health care practitioners’ characteristics (health care practitioners’
characteristics gender, race and ethnicity), and community resources (usual source of care
location and transportation mode). A Chi square analysis was used to identify differences
in usual source of care and insurance status between health condition groups. Eighteen
percent of the sample (n=109, 18%) did not identify their usual source of care. Most of
the participants (n=281, 45%) indicated their usual source of care was a health care
facility (e.g., hospital clinics or outpatient department); and there was no significant
difference between groups on usual source of care, X2 (6, N=513) =7.45, p=.281. Most of
the participants reported that they had private insurance (n=392, 63%); and there was a
significant difference between groups on insurance, X2 (4, N=622) =131.57, p<.01. Most
of the individuals with MD (n=56, 49%) and CM (n=20, 51%) had public insurance while
individuals with PI had private insurance (n=390, 83%).
A Chi square analysis was used to identify differences between groups on the
health care practitioner’s gender, race and ethnicity. There were no significant differences
between groups on health care practitioner’s gender, X2 (14, N=232) = 6.44, p=.169; race,
X2 (8, N=232) = 5.33, p=.721; and ethnicity, X2 (6, N=232) = 11.31, p=.079. Interestingly,
more than 60% of the participants did not report their health care practitioner’s
characteristics [e.g., gender (n=391, 63%), race (n=399, 64%) or ethnicity (n=395,
64%)]. Of those who did respond, the health care practitioners were most likely to be
male (n=189, 81%), White (n=154, 69%) and non-Hispanic (n=199, 88%).

64
A Chi square analysis was used to identify differences in usual source of care
location and transportation mode between individuals with MD, PI, and CM. Eighteen
percent (n=109, 18%) did not identify their usual source of care location and
transportation mode. Of those who did, most of the individuals indicated the office as
their usual source of care location (n=419, 82%) over the hospital clinic or emergency
room. The emergency room was the least used for the usual source of care location (n=3,
0.5%). There was no significant difference between groups on usual source of care
location, X2 (6, N=513) =7.44, p=.282. Most of the individuals were self-driven (n=416,
81%) to the usual source of care location. Walking to the usual source of care was the
least used transportation mode (n=17, 3%). Individuals with PI were more likely driven
to the usual source of care location (n=26, 5%) than riding a public transportation (n=15,
3%) while individuals with CM were more likely ride a public transportation than were
driven to the usual source of care location. There was a significant difference between
groups on transportation mode, X2 (8, N=513) =35.95, p <.01. See Table 4.3 for detailed
descriptive statistics of enabling resources.
Table 4-3
Descriptive Statistics for Enabling Resources
________________________________________________________________________

65
Enabling Resources Health Condition
___________________________________________
Variables MD (n=114, 18%) PI (n=469, 76%) CM (n=39, 6%)
n (%) n (%) n (%)
Usual Source of Care (Provider Type)
Facility 59 (21%) 202 (72%) 20 (7%)
Person 22 (14%) 132 (81%) 9 (5%)
Person in Facility 9 (13%) 55 (80%) 5 (7%)
Inapplicable*
Personal/Family Resources
Insurance Status
24 (22%) 80 (73%) 5 (5%)
Any Private 37 (9%) 340 (87%) 15 (4%)
Public Only 56 (58%) 41 (35%) 20 (17%)
Uninsured
Health Care Practitioners’ Characteristics
Health Care Practitioner’s Gender
21 (19%) 88 (78%) 4 (3%)
Male 25 (13%) 153 (81%) 11(6%)
Female 6 (14%) 34 (79%) 3 (7%)
Inapplicable*
83 (21%) 282 (72%) 25(7%)
Health Care Practitioner’s Race
White 20 (13%) 123 (80%) 11(7%)
Black 2 (11%) 16(89%) 0 (0%)
Asian 5 (13%) 32 (84%) 1 (3%)
Native American 1 (14%) 6 (86%) 0 (0%)
Other Pacific Islander 2 (33%) 4 (67%) 0 (0%)
Inapplicable* 84 (21%) 288 (72%) 27(7%)
Health Care Practitioner’s Ethnicity
Hispanic 1 (3%) 26 (93%) 1(4%) Non-Hispanic 28 (14%) 158 (79%)
13(7%)
Inapplicable* 85 (22%) 285 (72%) 25(6%)
(Table 4-3 Continues)
(Table 4-3 Continued)
_______________________________________________________________________
66
Enabling Resources Health Condition
___________________________________________
Variables MD (n=114, 18%) PI (n=469, 76%) CM (n=39, 6%)
n (%) n (%) n (%)
Community Resources
Usual Source of Care Location
Office 72 (17%) 322 (77%) 25(6%)
Hospital Clinics (not ER) 17 (19%) 66 (73%) 8(8%)
Hospital, Emergency Room 1 (33%) 1 (33%) 1(33%)
Inapplicable*
Transportation Mode
24 (22%) 80 (73%) 5(5%)
Self-driven 56 (13%) 336 (81%) 24(6%)
Is Driven 18 (38%) 26 (54%) 4(8%)
Public Transportation 12 (37%) 15 (47%) 5(16%)
Walk 4 (23%) 12 (71%) 1(6%)
Inapplicable* 24 (22%) 80 (73%) 5(5%)
*Inapplicable: Question skipped by participants
Health Behaviors
Health behaviors comprised health service uses (office-based clinic visits and
outpatient-based clinic visits) and health practice (smoking habit). The number of
officebased clinic visits (Mean= 4.1, SD=8.95, range 0-132) was significantly greater
than the number of outpatient hospital-based visits (Mean=0.29, SD=1.55, range 0-26).
Officebased clinics were much preferred over outpatient hospital-based clinics. A one-
way ANOVA indicated there was a significant difference in the office-based clinic visits
between groups, F (2, 2) =87.53, p=.000. Individuals with a CM reported the greatest
number of office-based clinic visits (Mean=14.94, SD=13.67) compared to individuals
67
with a MD (Mean=9.98, SD=16.24). Individuals with a PI reported the lowest number of
office based clinic visits (Mean=1.82, SD=1.99).
There were statistically significant differences in outpatient hospital-based clinic
visits, F (2, 2) =9.63, p =.000 between the three health condition groups. Individuals with
a MD had the highest number of outpatient hospital-based clinic visits (Mean=.789,
SD=3.22) compared to individuals with a CM (Mean=.14, SD=.63). Individuals with a PI
reported the lowest number of outpatient hospital-based clinic visits (Mean=.14, SD=.63).
See Table 4.4 for descriptive statistics of health services use.
Table 4-4
Descriptive Statistics of Health Services Use
Health Services Use
______95% CI_____
Variables M
SD LB UB
Total Office-Based Clinic Visits
Mental Disorder (MD) 9.9 16.2 6.9 12.9
Physical Illness (PI) 1.8 1.9 1.6 2.0
Co-morbid (CM) 14.9 13.6 19.5 19.3
Total Outpatient Hospital-Based Visits
Mental Disorder (MD) 0.78 3.2 0.19 1.3
Physical Illness (PI) 0.14 0.6 0.08 0.2
Co-morbid (CM) 0.71 1.6 0.19 1.2
A Chi square analysis indicated that there were statistically significant differences
between groups on smoking, X2 (6, N=622) = 60.04, p<.01. Most of the participants were
non-smokers (n=392, 63%). Interestingly, majority of the participants with a PI indicated
they were non-smokers (n=325, 83%) while majority of the participants with a MD
(n=51, 50.5%) and a CM (n=18, 51%) indicated they were smokers. There were 90
68
(14%) participants who did not indicate their smoking habit. See Table 4.5 for descriptive
statistics of health practice (smoking).
Table 4-5
Descriptive Statistics of Health Practice (Smoking)
________________________________________________________________________
Smoking Health Condition
Variable ________________________________________________
MD (n=114) PI (n=469) CM (n=39)
n (%) n (%) n (%)
Currently Smoke
Yes 51 (36%) 71 (51%) 18 (13%)
No 50 (13%) 325 (83%) 17 (4%)
Inapplicable* 13 (15%) 73 (81%) 4 (4%)
*Inapplicable: Question skipped by participants
Health Outcomes
Descriptive statistics for health outcomes (physical health status and mental health
status) were obtained and categorized according to participant’s self-identified health
conditions, (MD, PI, CM). A one-way ANOVA determined that there were no significant
differences in physical health status, F (2, 619) = .713, p=.490 between health condition
groups. There were significant differences in mental health status, F (2, 619) =21.68,
p=.000 between groups. The mental health status of individuals with PI was significantly
better than that of participants with MD. Participants with CM had a poorer mental health
status than those with PI and MD.
Not surprisingly, individuals with MD reported a better physical health status
(Mean=43.4; SD=18) than mental health status (Mean=33.7; SD=18.3). Similarly,
individuals with CM indicated that their physical health status (Mean=39.7; SD=20) was
69
better than their mental health status (Mean=31.5; SD, 17.8). Although individuals with
MD and those with CM indicated their physical health status was better than their mental
health status, these results were not significant (p=.490). As might be expected, mental
health status of individuals with PI (Mean=45.5; SD=20.8) was significantly higher than
their physical health status (Mean=43.6; SD=20.1). See Table 4.6 for the descriptive
statistics of health outcomes.
Table 4-6
Descriptive Statistics of Health Outcomes
Health Outcomes
Variables M
__95% CI_
SD LB UB
F p
Physical Health Status .713 .490
Mental Disorder 43.4 18 40.1 46.8
Physical Illness 43.6 20 41.8 45.4
Co-morbid 39.7 20 33.2 46.2
Mental Health Status 21.685 .000*
Mental Disorder 33.7 18.3 30.3 37.1
Physical Illness 45.5 20.8 43.6 47.4
Co-morbid 31.5 17.8 25.7 37.3
*p<.05
Results
Aim 1 Research Question 1 (A1R1)
A one-way multivariate analysis of variance (MANOVA) was conducted to
determine the effect of predisposing factors (health conditions (mental disorders, physical
illness , co-morbid mental disorders and physical illness)}, demographic factors {age,
gender, race, ethnicity, education, marital status}, socio-economic status {poverty status},

70
health attitudes and perceived health status {perceived health status, perceived
mental health status}) and enabling resources (usual source of care {provider type},
health care practitioner’s characteristics {health care practitioners’ gender, race and
ethnicity}, personal/family resources {insurance status}, and community resources {usual
source of care location and transportation mode})] on health behaviors (health services
use {office-based clinic visits and outpatient hospital-based clinic visits} and health
practice {smoking habit}). MANOVA results indicated that health conditions, Wilks’
Λ= .50, F(6, 54)=3.7, p=.003, partial η2=.212; ethnicity, Wilks’ Λ= .50, F(9, 65)=2.45,
p=.018, partial η2=.107, health attitudes, Wilks’ Λ= .126, F(42, 81)=2.0, p =.005, partial
η2=.238, perceived mental health status, Wilks’ Λ= .213, F(12, 72) =4.7, p=.000, partial
η2=.129, and usual source of care location, Wilks’ Λ= .738, F(3, 27) =3.2, p=.04, partial
η2=.024 had a significantly effect on the combined dependent variables of office-based
clinic visits, outpatient hospital-based clinic visits, smoking habit. However, multivariate
effect sizes are small.
Univariate ANOVA and Bonferroni post hoc tests were conducted as follow-up
tests. ANOVA results indicated that the DV office-based clinic visits significantly differs
for health conditions, F(2, 703) =5.94, p=.007, partial η2=.064, and perceived mental
health status F(4,769.48)=6.50, p=.001, partial η2=.079. ANOVA results also indicated
that the DV outpatient hospital-based clinic visits significantly differs for ethnicity, F(3,
3.805) =5.125, p=.006, partial η2=.205; and health attitudes F(14, 1.63) =2.192, p=.036,
partial η2=.402. The DV smoking significantly differs for health attitudes only, F(14,
1.794) =2.2, p=.034, partial η2=.182.
Bonferroni post hoc results for health services indicated that individuals with
mental disorders (MD) and co-morbid mental disorders and physical illness (CM)

71
preferred office-based clinics more than individuals with physical illness (PI). Individuals
with fair to excellent perceived mental health status were more likely to be non-smokers
than individuals with poor perceived mental health status. Individuals with poor
perceived mental health status preferred to visit office-based clinics than those with fair
to excellent perceived mental health status. Individuals who were self-driven to their
usual source of care were more likely to be non-smokers than individuals who walk and
use public transportation (i.e. taxis, bus and train). Non-Mexican Hispanics were more
likely to visit the outpatient hospital-based clinics than Black non-Hispanics and non-
Hispanics. Other relationships were non- significant. A1R1 was partially supported.
Aim 1 Research Question 2 (A1R2)
A one-way MANCOVA was conducted to determine the relationship of
population characteristics [(predisposing factors {health conditions (mental disorders,
physical illness, co-morbid mental disorders and physical illness)}, demographic factors
{age, gender, race, ethnicity, education, marital status}, socio-economic status {poverty
status}, health attitudes, and perceived health status {perceived health status, perceived
mental health status})], and health behaviors (health services use {office-based clinics
visits, outpatient hospital-based clinics visits}and health practice {smoking habit})
controlling for selected moderating factors, enabling resources (usual source of care
{provider type}, health care practitioner’s characteristics {health care practitioners’
gender, race and ethnicity and provider type}, personal/family resources {insurance
status} and community resources{usual source of care location and transportation
mode}). The main effects of marital status, Wilks’ Λ= .95, F(3, 138)=2.7, p=.049, and
perceived mental health status, Wilks’ Λ= .93, F(3, 138) =3.5, p=.018, had a significant
effect on the combined DV of health behaviors. The covariates [health care practitioner’s

72
gender and usual source of care, Wilks’ Λ= .92, F(3, 138)=4.031, p=.009; health care
practitioner’s gender and usual source of location, Wilks’ Λ= .88, F(3, 138) =6.031,
p=.001; usual source of care and transportation mode, Wilks’ Λ= .81, F(9, 336) =3.357,
p=.001; and health care practitioner’s gender, usual source of care and transportation
mode, Wilks’ Λ= .88, F(3, 138)=6.448, p=.000] significantly influenced the combined
DV of health behaviors.
Univariate ANOVA results indicated that only the dependent variable of smoking
was significantly effected by the covariate health care practitioner’s gender and usual
source of care, F (1, 10) =13.38, p=.002; health care practitioner’s gender and usual
source of care location, F (2, 29) =5.125, p=.006; usual source of care and transportation
mode, F (2, 29) =2.22, p=.034; and health care practitioner’s gender and usual source of
care, F (2, 29) =6.496, p=.000. After controlling for enabling resources only perceived
mental health status remained to have significant relationships with health behaviors.
Individuals with poor perceived mental health status preferred to visit office-based clinics
than those with fair to excellent perceived mental health status. Other effects were
nonsignificant. A1R2 was partially supported.
Aim 1 Research Question 3 (A1R3)
General linear model or a one-way multivariate analysis of variance (MANOVA)
was conducted to determine the relationship of population characteristics [(predisposing
factors{health conditions (mental disorders, physical illness, co-morbid mental disorders
and physical illness)}, demographic factors {age, gender, race, ethnicity, education,
marital status}, socio-economic status {poverty status}, health attitudes, and perceived
health status {perceived health status, perceived mental health status}, and enabling
resources (usual source of care {provider type}, health care practitioner’s characteristics

73
health care practitioners’ gender, race and ethnicity}, personal/family resources
{insurance status},and community resources {usual source of care location,
transportation mode})], health behaviors (health services use {office-based clinic visits,
outpatient hospital-based clinic visits}, health practice {smoking habit}), and health
outcomes (physical health status {physical component summary} and mental health
status {mental component summary}). MANOVA results indicated that health conditions,
Wilks’ Λ= .88, F (4, 186) =3.1, p=.017, perceived mental health status,
Wilks’ Λ= .81, F (8, 186) =2.4.7, p =.016, and usual source of care location, Wilks’
Λ= .81, F (2, 93) =10.58, p =.000, significantly influenced the combined dependent
variables of health outcomes (physical health status and mental health status).
Univariate ANOVA and Bonferroni post hoc tests were conducted as follow-up
tests. ANOVA results indicated that the DV mental health status significantly differed for
health conditions (mental disorders, physical illness, co-morbid mental disorders and
physical illness), F(2, 494) =5.5, p=.005; perceived mental health status, F(4, 300) =3.3,
p =.013; and usual source of care location, F(1, 1388) =15.51, p=.000. The DV physical
health status differed significantly for usual source of care location, F(1,1362)=14.47, p
=.000.
Bonferroni post hoc results for health outcomes indicated that individuals who
have mental disorders and those with a co-morbid mental disorder and physical illness
were more likely to have lower mental health status scores than those with a physical
illness condition only. Those whose perceived mental health status was not reported have
significantly lower mental health status scores than individuals who indicated their
perceived mental health status. Those whose usual source of care location was not
reported were more likely to have lower physical health status scores than those who

74
indicated office as their usual source of care location. Those whose usual source of care
location was not reported have significantly lower mental health status scores than those
who indicated the office and hospital clinics as their usual source of care location. Other
relationships were non- significant. A1R3 was partially supported.
Aim 1 Research Question 4 (A1R4)
A one-way MANCOVA was conducted to determine the relationship of
population characteristics [(predisposing factors (health conditions {mental disorders,
physical illness, co-morbid mental disorders and physical illness}, demographic factors
{age, gender, race, ethnicity, education, marital status}, socio-economic status {poverty
status}, health attitudes, and perceived health status {perceived health status, perceived
mental health status})], health behaviors (health services use {office-based clinic visits,
outpatient hospital-based clinic visits}and health practice {smoking habit}), and health
outcomes (physical health status {physical component summary}and mental health status
{mental component summary}) controlling for selected moderating factors [enabling
resources (usual source of care {provider type}, health care practitioner’s
characteristics{health care practitioners’ gender, race and ethnicity}, personal/family
resources {insurance status} and community resources {usual source of care location and
transportation mode})]. The main effects of health conditions, Wilks’ Λ= .94, F(2, 136)
=4.7, p=.011, race, Wilks’ Λ= .93, F(2, 136) =5.0, p=.008, perceived health status, Wilks’
Λ= .83, F(2, 136) =13.5, p=.000, perceived mental health status, Wilks’ Λ= .85, F(2,136)
=12.3, p=.000, and total office-based clinic visits, Wilks’ Λ= .89, F(2,136) =7.7, p=.001
had a significant effect on the combined DV of health outcomes (physical health status
and mental health status).

75
The covariates significantly influenced the combined DV of health outcomes,
usual source of care location, Wilks’ Λ= .92, F(2, 136) =5.7, p =.004; health care
practitioner’s gender and health care practitioner’s ethnicity, Wilks’ Λ= .905, F(6, 272)
=2.32, p=.034; health care practitioner’s gender and usual source of care location, Wilks’
Λ= .95, F(2, 136) =3.36, p=.36; and health care practitioner’s ethnicity and usual source
of care location, Wilks’ Λ= .91, F(4, 272) =3.33, p=.011. The ANOVA results indicated
that the dependent variable physical health status was significantly effected by health
conditions, F(1, 393) =6.53, p=.012, race, F(1, 605) =10, p=.002; perceived health status,
F(1, 1,546) =25.6, p=.000; perceived mental health status, F(1, 521) =8.65, p=.004;
office-based clinic visits, F(1, 877) =14.54, p=.000; the covariates usual source of care
location, F(1, 560) =9.3, p=.003; health care practitioner’s ethnicity, F(4, 172) =2.86,
p=.026; and the combined covariates health care practitioner’s gender and health care
practitioner’s ethnicity, F(3, 227) =3.76, p=.012; health care practitioner’s ethnicity and
usual source of care location, F(2, 391) =6.5, p=.002; and health care practitioner’s
gender, health care practitioner’s ethnicity and usual source of care location, F(1, 263)
=4.378, p=.038. The ANOVA results also indicated that the dependent variable mental
health status was significantly effected by health conditions, F(1, 535) =5.67, p=.019,
perceived mental health status, F(1, 824) =8.74, p=.004; office-based clinic visits, F(1,
469)=4.98, p=.027; the covariates usual source of care location, F(1, 504) =5.3, p=.022;
and the combined covariates health care practitioner’s gender and usual source of care
location, F(1, 582)=6.17, p=.014.
After controlling for enabling resources only perceived mental health status
remained to have significant relationship with health outcomes. Those whose perceived
mental health status was not reported had significantly lower mental health status scores

76
than individuals who indicated their perceived mental health status. Other effects were
non-significant. A1R4 was partially supported.
Aim 2 Research Question 1 (A2R1)
A Kruskal-Wallis test was conducted to evaluate the differences in usual source of
care between individuals with self-reported mental disorders and individuals without
mental disorders. The test, which was corrected for tied ranks, was non-significant, χ2 (2,
N= 622) =5.34, p=.069. The results of the tests indicated a non-significant difference
between the usual source of care and health conditions groups. The majority of
participants used a facility either the hospital clinic or the outpatient department as their
usual source of care (n=213, 54%). Individuals with MD preferred the hospital clinic or
outpatient department as their usual source of care (n=59, 66%) more than individuals
with PI (n=202, 52%) or CM (n=20, 58%). Individuals with PI preferred the provider
who works in the office as their usual source of care (n=132, 34%) more than the
individuals with MD (n=22, 24%) or CM (n=9, 33%). These differences were not
significant. A2R1 was not supported.
Aim 2 Research Question 2 (A2R2)
A one-way analysis of variance was conducted to evaluate the difference in
physical health status between individuals with self-reported mental disorders and
individuals without mental disorders. The independent variable was health conditions
(mental disorders, physical illness, co-morbid mental disorders and physical illness); the
dependent variable was the physical health status. The ANOVA was non-significant, F(2,
619) =.713, p=.490. There was no significant difference in the physical health status
means between the three health conditions groups. However, the mean of co-morbid
group was lower (M=39, SD=20) than the means for both MD group (M=43, SD=18) and

77
PI group (M=43, SD=20). This result indicated that individuals with self-reported mental
disorders did not differ in physical health status when compared to individuals without
mental disorder. A2R2 was not supported.
Aim 2 Research Question 3 (A2R3)
A one-way analysis of variance was conducted to evaluate the difference in
mental health status between individuals with self-reported mental disorders and
individuals without mental disorders. The independent variable was health conditions
(mental disorders, physical illness, co-morbid mental disorders and physical illness); the
dependent variable was the mental health status. The ANOVA was significant, F(2, 619)
=21.68, p=.000. The strength of relationship between health conditions and physical
health status, as assessed by η2 was weak, with the health conditions accounting for 6%
of the variance of the dependent variable.
Follow-up tests were conducted to evaluate pairwise differences among the
mental health status mean scores. Bonferroni post hoc comparisons indicated that there
were significant differences between in the mental health status mean scores between
groups. Individuals with PI (45.5, SD=20.82) had a higher mental health status score than
the individuals with MD (37.8, SD=18.3) and CM (31.52, SD=17.83). The 95%
confidence intervals for the pairwise differences, as well as the means and standard
deviations for the three health conditions are reported in Table 4.7. There was a
significant difference in mental health status between individuals with self-reported MD
(mental disorders only and co-morbid) and individuals without mental disorders (PI
only). Individuals with PI rated their mental health status better than individuals with
self-reported MD and individuals with CM. A2R3 was supported.
Table 4-7

78
95% Confidence Intervals of Pairwise Differences in Mean Mental Health Status
________________________________________________________________________
Mental Health Status M SD Mental Disorders Physical Illness
________________________________________________________________________
Mental Disorder 33.7 18.3
Physical Illness 45.5 20.8 6.7 to 16.84
Co-morbid 31.5 17.8 -11.26 to 6.74 -22.12 to -6.0
Summary
Multivariate analysis of variance (MANOVA) was used to analyze A1R1 and
A1R3 while multivariate analysis of covariance (MANCOVA) was used to analyze
A1R2 and A1R4. A univariate analysis of variance (ANOVA) was used to analyze A1R1,
A2R2 and A2R3. The sample (N=622) was categorized according to three health
conditions, mental disorder (n=114), physical illness (n=469) and co-morbid mental
disorder and physical illness (n=39). The sample was primarily male, White
nonHispanic, married, had high school diploma, middle to high income, had private
insurance; and was a non-smoker. Furthermore, the majority of the participants indicated
their perceived health status and perceived mental health to be “good” to “excellent”.
Most of the participants indicated facilities such as hospital clinics and outpatient
departments for their usual source of care (provider type). Most of the participants
reported positive health attitudes.
The majority of the participants who indicated their health care practitioners were
male, and non-Hispanic White. Most of the participants identified the office-based clinics
as their usual source of care location and self-driven as their transportation mode. There
were more office-based clinic visits than the outpatient hospital-based clinic visits for

79
health care services. Individuals with physical illness reported that their mental health
status was better than their physical health status.
Aims A1R1, A1R2, A1R3 to A1R4 were partially supported as some significant
relationships existed among the study variables. Perceived mental health status remained
significant on health behaviors and health outcomes after controlling for enabling
resources. Individuals with poor perceived mental health status preferred office-based
clinics than those with fair to excellent perceived mental health status. Those whose
perceived mental health status was not reported had significantly lower mental health
status scores than individuals who indicated their perceived mental health status.
Although some significant relationships were found between the variables analyzed in
A2R1 to A2R2, the main premises of the research questions were not supported as there
were no significant differences in usual source of care and physical health status between
individuals with self-reported mental disorders and individuals without mental disorders.
Aim A2R3 was supported. A significant difference was found in mental health status
between individuals with self-reported mental disorders and individuals without mental
disorders. Individuals with CM were more likely to have a poorer mental health status
than individuals with PI or MD.

CHAPTER V
Discussion and Conclusion
This chapter contains a discussion of findings of this study and comments on the
usefulness of the Modified Behavioral Model of Health Services Use model guiding the
study. Limitations of the study are presented. Nursing implications and recommendations
for future research are discussed.
Discussions of Findings
Modified Behavioral Model of Health Services Use (BMHSU)
This study utilized Modified Behavioral Model of Health Service Use
(BMHSU) to explore and understand the relationships of predisposing factors, enabling
resources, health behaviors and health outcomes as well as differences in usual source of
care and health outcomes between individuals with self-reported mental disorders and
those without mental disorders. In this study, the BMHSU framework described the
complexity of determining health outcomes and gave directions to the study analyses
(MANOVA, MANCOVA, and ANOVA). The application of BMHSU was useful in
examining the relationships of population characteristics, health behaviors and health
outcomes of individuals with self- reported mental disorders and individuals without
mental disorders.

81
82
Sample
The sample of this study was predominantly male, White, married, with a high
school diploma, and middle to high income status. This sample is representative of the
total U.S. population for race, marital status and poverty status but not for gender and
education. According to the U.S. Census Bureau (2010), the current U.S. population is
predominantly females (50.4%), White (74%), married (50.3%), with some college
education (41%), and a middle to high income (51%). Education level is somewhat
higher in the national U.S. population than the sample in this study. Similarly, Zeber, et
al.’s (2009) sample of Veterans with mood disorders (N=435) was predominantly White
(n=336, 77.3%) male (n=373, 85.7%); however they differed on regards to marital,
education and income status. In the Veteran’s sample, a lower percentage of participants
reported being married (n=131, 30.2%) than this study. In addition, Zeber’s sample
reported some college education (n=299, 68%) and low income status (n=154, 59.9%) in
contrast with the results of this study. This profile is in sharp contrast to most studies on
health outcomes among individuals with mental health conditions wherein the sample
was predominantly female, non Hispanic, White, and 35 to 54 years old, with a low to
middle income status (Bandeira et al., 2008; Keyes et al., 2008). The difference in sample
characteristics can be partly explained by the fact that this study included persons that did
not report a mental disorder.
The findings in this study contradict the findings of Kass et al. (2007) on attitudes
related to health insurance and the health care system. Individuals with chronic medical
conditions were more likely to have health insurance (95%); however, they reported
being denied coverage by insurance companies because of their current medical condition

82
(Kass et al., 2007). On the other hand, Machlin and Carper (2005) reported no significant
differences in the health attitudes for those individuals with private and public insurance.
Also the uninsured population between the ages of 18 and 64 years perceived that they
were healthy, did not need health insurance and insurance was not worth the cost
(Machlin & Carper, 2005).
In Al-Windi’s study (2005), most respondents with health conditions (e.g.,
hypertension, psychiatric disorders, musculoskeletal disease) reported poor perceived
health status. Perceived health status was influenced by demographic characteristics (i.e.
age, gender, employment). Female participants, 45-64 years old, and unemployed were
more likely have poor perceived health status. Life satisfaction with health was the
strongest predictor of poor perceived health status (Al-Windi, 2005). Although
participants in this study were more likely have perceived health status higher than
AlWindi participants, further research is needed to clarify the direction of association
between demographic characteristics and perceived health status. The differences in the
relationship of age, gender, and health conditions reflect variations in the sample
characteristics of these studies suggesting that a more detailed examination of sample
characteristics including geographical location would be beneficial to better describe the
sub-samples and determine their needs.
Enabling Resources
Carper and Machlin (2009) reported that individuals without usual source of care
and insurance were more likely to have issues accessing medical care. Additionally, Xu
(2002) implied that individuals with usual source of care were more likely to have a
regular physician, use preventive services and access health services than those without
usual source of care. In this study, facility (e.g., hospital clinics and outpatient

83
department) was the preferred usual source of care. However, other facilities (i.e., urgent
care centers, retail clinics) were used as usual source of care in other studies (Weinick et
al., 2010). Determining the preferred usual source of care for patients with MD in various
locations would give directions to strategies for assuring health care access.
Findings of this study indicated there were no significant differences in health
care practitioner’s characteristics (gender, race, ethnicity) among individuals with MD, PI
and CM. Additionally, there was no significant relationship of health care practitioner’s
characteristics to health outcomes on individuals with health conditions. Similarly,
Kearns and Ji (2007) reported that there were no significant relationships of
patientprovider gender/racial/ethnic concordance, health services use and health
outcomes among Florida Medicaid recipients. Additionally, Johnson et al. (2004) stated
that racial ethnic differences did not fully explain the differences in demographic factors,
health status, usual source of care, patient-provider concordance between racial-ethnic
groups; and other factors must be considered that include cultural competence and
language related bias perceptions.
Rubin, Peyrot, and Siminerio (2006) found the quality of patient-provider
collaboration was the strongest predictor of patient outcomes among individuals with
diabetes. In this study, access to providers was significantly associated with positive
patient outcomes. Strategies of effective patient-provider collaboration must be given
priority to address the physical and the psychosocial needs of individuals with physical
illness, mental disorders and co-morbidity and would enhance patient outcomes.
Studies that focus on the relationships of provider-patient concordance and patient
outcomes or the influence of health care practitioner’s characteristics to patient outcomes
need further investigation. Interpretations of relationships and effects of variables to

84
patient outcomes are highly inconclusive but the results can be used to either support or
refute hypotheses in future studies that focus on provider’s characteristics (gender, race
and ethnicity). Future research must also include cultural competence among health care
providers to address the existing racial ethnic disparities among diverse populations with
health care needs (Park & Grindel, 2007; Perilla, Norris, & Lavizzo, 2002).
Health Behaviors
Similar findings of this study on health services use and health practice (smoking)
were noted from previous studies. The study of Ahmed and Fincham (2010) had similar
findings with this study on health services use. The office-based clinic visits was the most
preferred for health services.
In this study, 63% of the sample was non-smoker. Carper and Machlin (2005)
reported that out of the 43.6 million U.S. civilian noninstitutionalized population in 2003,
78.3% have indicated themselves as non-smokers (Carper & Machlin, 2005). In this
study, the non-smokers were predominantly among individuals with physical illness,
similar to the findings of Coultas et al. (2007).
Health Outcomes
Sareen et al. (2006) reported that co-morbid mental disorder and physical illness
(CM) was associated significantly with poor health outcomes. Similarly, the findings of
this study indicated that individuals with CM had the poorest health outcomes (physical
health status and mental health status) compared to their counterparts (individuals with
MD and PI). Additionally, the findings of Sorkin, Tan, Hays, Mangione, and
NgoMetzger (2008) reported that individuals with mental disorders significantly have
poorer mental health status than those with physical illness. Individuals with physical
illness reported poorer physical health status than the individuals with mental disorders

85
and no significant differences in physical health status between health conditions. These
results were similar with the findings of this study.
Findings from this study indicated that there was a significant relationship
between smoking and perceived mental health status. Individuals with fair to excellent
perceived mental health status were more likely to be non-smokers than individuals with
poor perceived mental health status. McLeish, Zvolensky, Smits, Bonn-Miller, and
Gregor (2007) found poorer perceived mental health status but no significant relationship
between smoking and perceived mental health status. The sample consisted of females,
young, college education, and daily smoker (McLeish et al., 2007). Differences in gender,
age, education and smoking habit may have contributed to contradictions in these two
studies.
Findings in this study suggested that individuals with poor perceived mental
health status preferred to visit office-based clinics than those with fair to excellent
perceived mental health status. Hwang and Henderson (2010) found that majority of the
homeless individuals who have poor perceived mental health status used the emergency
department as their usual source of care contrary to the findings of this study. The
differences in the results of these two studies were more likely due to the variations in the
sample characteristics (e.g., insurance status, poverty status, health conditions).
Similar to findings by Devoe, Wallace and Fryer (2009) and Stagnitti (2009), our
study found that non-Mexican Hispanics were more likely to visit the outpatient
hospitalbased clinic than Black non-Hispanics and non-Hispanics. Stagnitti (2009)
reported a recent pattern that showed an increasing use of outpatient hospital-based clinic
by Black non-Hispanics in order to acquire prescription analgesics. One suggestion
regarding the use of outpatient hospital-based clinics was to be attentive to individual

86
patient characteristics and health care needs in order to provide better patient outcomes in
a given health care setting.
Significant differences were found between usual source of care location and
health outcomes (physical health status and mental health status). Provider’s offices were
the preferred location for usual source of care. The individuals who preferred the
provider’s offices were more likely to have better health outcomes. Similarly, Hwang and
Henderson (2010) reported that homeless adults used office-based clinics more frequently
than the emergency rooms for medical treatment and were more likely to report
satisfaction with care. Harrison et al. (2008) asserted that the key factor to improved
health outcomes is contingent upon the delivery of evidence-based practice provided by
qualified health care practitioners and not the location of usual source of care.
Findings from this study indicated that after controlling for enabling resources
(health services, smoking), a significant relationship between perceived mental health
status and health behaviors remained. Individuals with poor perceived mental health
status preferred office-based clinics. Similarly, Ralph-Campbell, Pohar, Guirguis, and
Toth (2006) reported individuals with poor perceived mental health status sought
treatment in a physician’s office or an emergency room. Poor access to mental health
clinics and lack of culturally sensitive treatment programs were reasons for the disparities
in location of health services and treatment.
Additionally, after controlling for enabling resources (health services, smoking), a
significant relationship between perceived mental health status and health outcomes
remained. Individuals who did not report their perceived mental health status had
significantly lower mental health status scores than individuals who indicated their
perceived mental health status. Findings from this study suggested that individuals who

87
rated their perceived mental health status good to excellent were more likely to have
better mental health status than those who rated their perceived mental health status poor.
Several studies support the relationship of perceived mental health status and mental
health status (Cole, 2007; Overland, Glozier, Maeland, Aaro, & Arnstein, 2006). Weinick
et al. (2006) reported that individuals who rated their perceived mental health status as
poor had difficulty accessing usual source of care resulting in poor mental health status.
Rhoades (2004) also reported that individuals with poor perceived mental health status
deteriorated their physical and mental health status eventually due to issues on accessing
usual source of care.
The provider’s office was the preferred usual source of care for individuals with
self-reported mental disorders and those individuals without mental disorders. Similarly,
Garibaldi, Conde-Martel, and O’Toole (2005) found no differences in usual source of
care in individuals with mental disorders or physical illness. The samples in this study
and the Garibaldi et al. (2005) study were similar as both samples reported a moderate to
high income and had health care insurance. Most studies that reported significant
differences in the usual source of care were conducted with persons who had limited or
no health insurance coverage and/or a low income (O’Toole, Gibbon, Hanusa, Fine,
1999; Richardson & Norris, 2010; Waidman & Rajan, 2000).
In this study, findings on physical health status are inconsistent with other studies
in that there is an association of chronic health conditions with poor physical health status
(Brown, Ang, & Pebley, 2007). No significant differences were reported on physical
health status between individuals with self-reported mental disorders and those without
mental disorders. Philipps, Hammock, and Blanton (2005) reported that a college
education, non-Hispanic ethnicity, health insurance and a higher income were associated

88
with good to excellent rating on physical health status. Although the participants in this
study were not as likely to have a college education, they were likely to have a high
school diploma, with health insurance and a middle to high income. In addition, the
sample in this study was primarily White, non-Hispanic.
Consistent with other studies, individuals with health conditions were
significantly different in mental health status and perceived mental health status.
Individuals with MD and/or CM who perceived their mental health status as poor also
reported worsening mental health status (Straus et al., 2009). Individuals with a physical
illness perceived their mental health status as good to excellent and they also reported
better mental health status than individuals with mental disorders. Individuals with
physical conditions would be expected to rate their perceived mental health and mental
health outcome higher than their physical health because of their existing physical needs
(Mozumdar & Roy, 2010).
Limitations of the Study
Generalization of the findings of this study is limited because the sample was
predominantly White with a moderate to high income; these results may not be applicable
to other racial-ethnic groups or marginalized individuals. Additionally, these results
cannot be generalized to individuals younger than 18 years old or older than 66,
individuals who are institutionalized, or individuals with illnesses or diseases that were
excluded from the study (e.g., terminal illnesses, personality disorders, and dementia).
Relying on self-reported data inherent in surveys such as MEPS can be problematic
because of the possibility of reporting errors or inaccuracies in the data that could
compromise the results. In addition, cross-sectional designs such as used in this study
describe a single time period; longitudinal studies that follow participants overtime

89
would provide a better understanding of health care practices and health outcomes.
Causal relationships are difficult to establish with cross-sectional designs; however, the
complexity of the issues of health care access, health behaviors and health outcomes can
best be studied with exploratory correlational designs.
Nursing Implications
The potential implications of this study are relevant to nursing education, clinical
practice, and research. Nurse educators can use the BMHSU model to explain the
numerous factors that affect health practice and outcomes so students are aware of the
barriers that can impact potential outcomes. Awareness of the complexity of the
relationship of these factors will support nursing interventions that eliminate barriers to
care and promote better health practices and outcomes. In doing so disparities related to
health care can be eliminated and morbidities and mortalities among individuals with
mental disorders (MD) will be reduced.
Knowledge about the strategies to reduce health care barriers and health services
use disparities among individuals with MD, PI, and CM is not enough. Follow through
actions relevant to the care of these population are needed. The development and testing
of innovative nursing interventions that are designed to remove barriers to health care
services will reduce disparities in care and facilitate better health practices and outcomes.
Such interventions would benefit persons with mental illness as they are often
marginalized in the current health system. Finally, nurses must take an active role in the
development and implementation of healthcare policies that facilitate access to healthcare
and assure health care disparities are not inflicted on marginalized individuals.

90
Recommendations for Future Research
Community based descriptive research that examines the factors affecting health
practices and outcomes of persons with mental disorders would give highlights to the
unique care needs and barriers within the community and provide direction to the
implementation of interventions that would assure quality health care services to personal
with mental disorders thus improving patient outcomes. Prospective longitudinal research
studies can refine our understanding about the relationship between environment,
population characteristics, health behaviors and health outcomes. Further exploration of
factors associated with health care services use, health behaviors, and health outcomes is
suggested to set the stage for intervention studies that will assure access to care and
improved health outcomes.
Summary
The results of this study add insights into the perceived health status, usual source
of care, health behaviors and health outcomes of persons with mental disorders. The
application of BMHSU was useful in examining the relationships of population
characteristics, health behaviors and health outcomes as well as the differences in usual
source of care, physical health status and mental health status between individuals with
self- reported mental disorders and those without mental disorders. The sample in this
study consisted predominantly of White, male, non-Hispanic, high school graduates, and
middle to high income status. The results provided support for the impact of perceived
mental health status on health behaviors and health outcomes. The findings that there
were no statistically significant differences in the usual source of care and physical health
status between individuals with mental disorders and those without mental disorders

91
suggest the need for further exploration to either support or refute these findings. The
results provided support for the significant differences in mental health status between
individuals with mental disorders and those without mental disorders. Individuals with PI
were more likely have higher perceived mental health status and better mental health
status than those individuals with mental disorders.
References
Adler, N., & Stewart, J. (2010). Health disparities across the lifespan: Meaning, methods
and mechanisms. Annals of the New York Academy of Science, 1186, 5-23.
Ahmed, A., & Fincham, J. (2010) Physician office vs. retail clinics: Patient preferences in
care seeking for minor illnesses. Annals of Family Medicine, 8(2), 117-123.
Al-Windi, A. (2005). The relations between symptoms, somatic and psychiatric
conditions, life satisfaction and perceived health. A primary care based study.
BioMed Central, 3(28). doi:10.1186/1477-7525-3-28
Andersen, R., & Aday, L. (1978). Access to medical care in the U.S.: Realized and
potential. Medical Care, 16(7), 533-546.
Andersen, R. (1995). Revisiting the behavioral model and access to medical care: Does it
matter? Journal of Health and Social Behavior, 36(March), 1-10.
Anderson, K., Balderramas, S., Davidson, J., De Maria, P., Eells, G., Greenleaf, C.,
Himmel, J., Levine, H., Readdean, K., Vincent, D., & Wyatt, J., (2010).
Considerations of integration of counseling and health services on college and
university campuses. Journal of American College Health, 58(6), 583-596.
Bandeira, F., Pereira, D., Arif, A., Dodge, B. & Asai, N. (2008). Race/ethnicity, income,
chronic asthma, and mental health: a cross sectional study using the behavioral
risk factor surveillance system, Psychosomatic Medicine, 70, 77-84.

92
Barrio, C., Palinkas, L., Yamada, A., Fuentes, D., Criado, V., Garcia, P., & Jeste, D.
(2008). Unmet needs for mental health services for Latino older adults:
Perspectives from consumers, family members, advocates and service providers.
Community Mental Health, 44, 57-74.
Benerjee, R., Ziegenfuss, J., & Shah, N. (2010). Impact of discontinuity in health
insurance on resource utilization. BioMed Central Health Services Research, 10,
195.
Bethel, J., Foreman, A., & Burke, S. (2011). Disaster preparedness among medically
vulnerable populations, American Journal of Preventive Medicine, 40(2), 139-
143.
Brown, A., Ang, A., & Pebley, A. (2007). The relationship between neighborhood
characteristics and self-rated health for adults with chronic conditions. American
Journal of Public Health, 97(5), 926-932.
Brunero, S., & Lamont, S. (2010). Health behavior beliefs and physical health risk factors
for cardiovascular disease in an outpatient sample of consumers with a severe mental
illness: A cross sectional survey. International Journal of Nursing Studies,
47, 753-760.
Burgos, A., Schetzina, K., Dixon, B., & Mendoza, F. (2005). Importance of generational
status in examining access to and utilization of health care services by Mexican
American children. Pediatrics, 115, 322-330. doi:10.1542/peds.2004-1353
Calton, T., & Arcelus, J. (2003). Adolescent units: A need for change? The Psychiatrist
27(3), 292-300.
Carper, K., & Machlin, S. (2005). Variations in smoking by selected demographic,
socioeconomic, insurance, and health characteristics, United States, 2003.

93
Statistical Brief # 101. October 2005. Agency for Health Care Research and Quality,
Rockville. Md. Retrieved from http://meps.ahrq/gov/mepsweb/data_files/
publications/st101/stat101.pdf
Carper, K., & Machlin, S. (2009). Variations in perceived need and access to specialist
care among Adults in the U.S. civilian noninstitutionalized population, 2007.
Statistical Brief #274. Agency for Healthcare Research and Quality, Rockville, MD.
Retrieved from
http://www.meps.ahrq.gov/mepsweb/data_files/publications/st274/stat274.shtml
Centers for Disease Control and Prevention (2010). International Classification of
Diseases, Ninth Revision, Clinical Modification (ICD-9-CM) Retrieved from
http://www.cdc.gov/nchs/icd/icd9cm.htm
Chen, S., Barnett, P., Sempel, J., & Timko, C. (2006). Outcomes and costs of matching
the intensity of dual-diagnosis treatment of patients’ symptom severity. Journal of
Substance Abuse Treatment, 31, 95-105.
Cheng, T. (2005). The impact of welfare reforms, health and insurance status on welfare
recipients’ health care access. Journal of Health Care for the Poor and
Underserved, 16(3), 588-601.
Cohen, S. B. (2009). Attitudes toward health insurance and their persistence over time,
adults 2006-2007. Statistical brief #260. Agency for Healthcare Research and Quality,
Rockville, MD. Retrieved from
http://www.meps.ahrq.gov/mepsweb/data_files/publications/st260/stat260.shtml Cole, P.
(2007). Black women and sickle cell disease: Implications for mental health
disparities research. Californian Journal of Health Promotion, 5, 24-39

94
Cooper, L., & Powe, N. (2004). Disparities in patient experiences, health care
processes, and outcomes: The role of patient-provider racial, ethnic, and
language concordance. The Commonwealth Fund. Retrieved from
www.cmwf.org
Coultas, D., Edwards, D., Barnett, B., & Wludyka, P. (2007). Predictors of depressive
symptoms in patients with COPD and health impact. COPD: Journal of Chronic
Obstructive Pulmonary Disease, 4, 23-28.
Cummings, S., & Cassie, K. (2008). Perceptions of biopsychosocial services needs
among older adults with severe mental illness: Met and unmet needs. Health &
Social Work, 33(2), 133-143.
Dawson, D., Grant, B., Chou, P. & Stinson, F. (2007). The impact of partner alcohol
problems on women’s physical and mental health. Journal of Studies on Alcohol
and Drugs, 68, 66-75.
Desai, M., Rosenheck, R., & Craig, T. (2005). Screening for alcohol use disorders among
medical outpatients: The influence of individual and facility characteristics.
American Journal of Psychiatry, 162(8), 1521-1526.
Devoe, J., Wallace, L., & Fryer, G. (2009). Measuring patients’ perceptions of
communication with healthcare providers: Do differences in demographic and
socioeconomic characteristics matter? Health Expectations, 12, 70-80.
Everett, A., Mahler, J., Biblin, J. Ganghuli, R., & Mauer, B. (2008). Improving the health
of mental health consumers. International Journal of Mental Health, 37(2), 8-48.
Ferguson, C. (2009). An effect size primer: A guide for clinicians and researchers.
Professional Psychology Research and Practice. doi: 10 1037/a0015808

95
Finney Rutten, L., Wanke, K., & Augustson, E. (2005). Systems and individual factors
associated with smoking status: Evidence from HINTS. American Journal of
Health Behavior, 29(4), 302-310.
Fleishman, J. (2010), Deriving SF-12v2 physical and mental health summary scores: a
comparison of different scoring algorithms. Quality of Life Research, 19(2), 231-
241.
Flynn, L., Budd, M. & Modelski, J. (2008). Enhancing resource utilization among
pregnant adolescents. Public Health Nursing, 25(2), 140-148.
Garland, A., Hough, R., Landsverk, J., McCabe, K., Yeh, M., Ganger, W., & Reynolds,
B. (2000). Racial and ethnic variations in mental health care utilization among
children in foster care. Children’s Services: Social Policy, Research, and
Practice, 3(3), 133-146.
Garland, A., Lau, A., Yeh, M., McCabe, K., Hough, R., & Landsverk, J. (2005). Racial
and ethnic differences in utilization of mental health services among high-risk youths,
The American Journal of Psychiatry, 162(7), 1336-1343.
Garrett, B., & Yemane, A. (2006). Racial and ethnic differences in insurance coverage
and health care access and use: a synthesis of findings from the assessing the new
Federalism project. The Urban Institute. Retrieved from
http://www.urban.org/UploadedPDF/311321_DP06-01.pdf
Garibaldi, B., Conde-Martel, A., & O’Toole, T. (2005). Self-reported comorbidities,
perceived needs, and sources for usual care for older and younger homeless
adults. Journal of General Internal Medicine, 20, 726-730.
Gelberg, L., Andersen, R., & Leake, B. (2000). The behavioral model for vulnerable
populations: Application to medical care use and outcomes for homeless people.

96
Health Service Research, 34(6), 1273-1302.
George, D., & Mallery, P. (2003). SPSS for Windows step by step: A simple guide and
reference. 11.0 update (4th ed). Boston: Allyn & Bacon.
Gill, K., Murphy, A., Zechner, M., Swarbrick, M., & Spagnolo, A. (2009). Co-morbid
psychiatric and medical disorders: Challenges and strategies. Journal of
Rehabilitation, 75(3), 32-40.
Goodwin, R., & Andersen, R. (2002). Use of the behavioral health care model of health
care use to identify correlates of use of treatment for panic attacks in the
community. Social Psychiatry and Psychiatric Epidemiology, 37, 212-219.
Grella, C., & Stein, J. (2006). Impact of program services on treatment outcomes of
patients with comorbid mental and substance use disorders, Psychiatric Services,
57(7), 1007-1015.
Gupta, R., de Wit, M., & McKeown, D. (2007). The impact of poverty on the current and
future health status of children. Pediatric Child Health, 12(8), 667-672. Hahm, H.,
Speliotics, A., & Bachman, S. (2008). Failure to receive health care among people
with mental illness: Theory and implications. Journal of Social Works in
Disability and Rehabilitation, 7(2), 94-111.
Harrison, M., Graham, I., Lorimer, K., VandenKerhof, E., Buchanan, M., Wells, P.,
Brandys, T., & Pierscianowski, T. (2008). Nurse clinic versus home delivery of
evidence-based community leg ulcer care: A randomized health services trial.
BioMed Central Health Services Research, 8, 243-253. doi:10.1186/1472-6963-
8-243.

97
Herson, J., & Snyder, D. (2011). Health insurance in America after the reform. The
Futurist, 20-22.
Hill, C., Gill, T., Taylor, A., Daly, A., Grande, E. & Adams, R. (2007). Psychological
factors and quality of life in arthritis: A population-based study. Clinical
Rheumatology, 26, 1049-1054.
Hwang, S., & Henderson, M. (2010). Health care utilization in homeless people:
translating research into policy and practice. Agency for Health Care Research
and Quality Working Paper No. 10002. Retrieved from
http://www.meps.ahrq.gov/mepsweb/data_files/publications/workingpapers/wp_1
0002.pdf
Jang, Y., Chiroboga, D., & Okasaki, S. (2009). Attitudes towards mental health services:
age group differences in Korean American adults. Aging & Mental Health, 13(1)
127-134.
Jano, E., Johnson, M., Chen, H., & Aparasu, R. (2008). Determinants of atypical
antipsychotic use among antipsychotic use among antipsychotic users in community-
dwelling elderly, 1996-2004. Current Medical Research and
Opinions, 24(3), 709-716.
Javier, J., Huffman, L., Mendoza, F., & Wise, F. (2010). Children with special health care
needs: how immigrant status is related to health care access, health care utilization,
and health status. Maternal Child Health Journal, 14, 567-579. Jofre-Bonet, M., Busch,
S., Falba, T., & Sindelar, J. (2005). Poor mental health and smoking: Interactive impact
on wages. Journal of Mental Health Policy and Economics, 8, 193-203.
Johnson, R., Saha, S., Arbelaez, J., Beach, M. & Cooper, L. (2004). Racial and ethnic
differences in patient perceptions of bias and cultural competence in health care.
Journal of General Internal Medicine, 19, 101-110.

98
Kane, D., Zotti, M., & Rosenberg, D. (2005). Factors associated with health care access
for Mississippi children with special health care needs. Maternal and Child
Health Journal, 95(2), S23-S31.
Kass, N., Medley, A., Natowicz, M., Hull, S. C., Faden, R., Plantings, L., & Gostin, L.
(2007). Access to health insurance: experiences and attitudes of those with genetic
versus non-genetic medical conditions, American Journal of Medical Genetics, Part A,
143, 707-717.
Kearns, W.D. & Ji, Y. (2007). Provider effects on racial/ethnic disparity in the Florida
Medicaid population. Louis de la Parte Florida Mental Health Institute.
University of South Florida, Tampa, FL
Keizer, I., Gex-Fabry, M., Eytan, A. & Bertschy, G. (2009). Smoking in psychiatric
inpatients: Association with working status, diagnosis, comorbid substance abuse
and history of suicide attempts. Addictive Behavior, 34, 815-820.
Keyes, K., Hatzenbuehler, M., Alberti, P., Narrow, W., Grant, B., & Hasin, D. (2008).
Service utilization differences for axis I psychiatric and substance use disorders
between white and black adults. Psychiatric Services, 59(8), 893-901.
Kline, J., & Mehler, K. (2006). Diagnostic inaccuracy and substance abusing patients
with comorbid mental disorders: A brief report. Journal of Dual Diagnosis, 2(3),
101-108.
Kilbourne, A., Andersen, R., Asch, S., Nakazono, T., Crystal, S., Stein, M., Gifford, A.,
Bing, E., Bozzette, S., Shapiro, M., & Cunningham, W. (2002). Response to
symptoms among a U.S. national probability sample of adults infected with
human immunodeficiency virus. Medical Care Research and Review, 59(1), 36-
58.

99
Kilbourne, A., Post, E., Nossek, A., Sonel, E., Drill, L., Cooley, S., & Bauer, M. (2008).
Service delivery in older patients with bipolar disorder: A review and
development of a medical care model. Bipolar Disorder, 10, 672-683.
Lamkaddem, M., Spreeuwenberg, P., Deville, W., Foets, M., & Groenewegen, P. (2008).
Changes in health and primary health care use of Moroccan and Turkish migrants
between 2001 and 2005: A longitudinal study. BioMed Central Public Health,
8(40). doi:10.1186/471-2458-8-40
Larson, C. (2002). Use of the SF-12 instrument for measuring the health of homeless
people. Health Services Research, 37(3), 733-750.
Lawrence, D., Mitrou, F., & Zubrick, S. (2009). Smoking and mental illness: results from
population surveys in Australia and the United States. BioMed Central Public
Health, 9(285). Retrieved from http://www.medscape.com/viewarticle/713661_5
Ledoux, T., Barnett, M., Garcini, L., & Baker, J. (2009). Predictors of recent mental
health service use in medical population: Implications for integrated care. Journal
of Clinical Psychology in Medical Settings, 16, 304-310.
Legorreta, A., Metz, D., Nelson, C., Ray, S., Chernicoff, H., & DiNubule, N. (2004).
Comparative analysis of individuals with and without chiropractic coverage,
Archive of Internal Medicine, 165, 1985-1992.
Lund, C., Breen, A., Flisher, A., Kakuma, R., Corrigall, J., Joska, J., Swartz, L., & Patel,
V. (2010). Poverty and common mental disorders in low and middle income
countries: A systematic review. Social Science & Medicine, 71, S17-S28.
Machlin, S., & Carper, K. (2005). Attitudes toward health insurance among adults age 18
and over, 1987 and 2002. Statistical brief #87. Agency for Healthcare Research
and Quality, Rockville, MD. Retrieved from
http://meps.ahrq.gov/mepsweb/data_files/publications/st87/stat87.pdf

100
McGuire, J., Gelberg, L., Blue-Howells, J., & Rosenheck, R. (2009). Access to primary
care for homeless Veterans with serious mental illness or substance abuse: A
follow-up evaluation of co-located primary care and homeless social services.
Administration and Policy in Mental Health and Mental Health Services
Research, 36(4), 255-264.
McKeown, M., & Colman, B. (2006). Monitoring physical health in people with mental
illness. Practice Nurse, 32(9), 15-18.
McLeish, A., Zvolensky, M., Smits, J., Bonn-Miller, M., & Gregor, K. (2007).
Concurrent associations between anxiety sensitivity and perceived health and
health disability among young adult daily smokers, Cognitive Behavior Therapy,
36(1), 1-11. doi:10.1080/16506070600794653
Medical Expenditure Panel Survey (2008). MEPS HC-105: 2006 full year consolidated
data file. Retrieved from
http://meps.ahrq.gov/mepsweb/data_stats/download_data/pufs/h105/h105doc.sht
ml
MEPS Medical Condition (2010). MEPS HC-104: 2006 Medical Condition. Agency for
Healthcare Research and Quality, Rockville, Md. Retrieved from
http://meps.ahrq.gov/mepsweb/data_stats/download_data/pufs/h104/h104doc.sht ml
MEPS (2010). Survey Background. Retrieved from
http://www.meps.ahrq.gov/mepsweb/about_meps/survey_back.jsp
Miranda, J., McGuire, T., Williams, D., & Wang, P. (2008). Mental health in the context
of health disparities. American Journal of Psychiatry, 165(9), 1102-1108.

101
Monheit, A., Cantor, J., DeLia, D., & Belloff, D. (2011). How have state policies to
expand dependent coverage affected the health insurance status of young adults,
Health Services Research, 46(1), 251-267.
Mozumdar, A., & Roy, S. (2010). Depression in adult males with lower extremity
amputation and its bio-social correlates. Health, 2(8), 878-889.
Muller-Oerlinghausen, B., Berghofer, A., & Bauer, M. (2002). Bipolar disorder. The
Lancet, 350(9302), 241-247.
Munro, B. (2001). Differences among group means: Multifactorial analysis of variance.
Statistical Methods for Health Care Research (4th ed.). Philadelphia: Lippincott.
National Center of Health Statistics Healthy People 2010. (2010). Mental health and
mental disorders. Retrieved from
http://www.healthypeople.gov/document/html/volume2/18mental.htm
National Institute of Mental Health. (2010). Statistics. Retrieved from
http://www.nimh.nih.gov/health/topics/statistics/index.shtml
Ndetan, H., Evans, M., Bae, S., Felini, M., Rupert, R., & Singh, K. (2010). The health
care provider’s role and patient complicance to health promotion advice from the
user’s perspective: Analysis of the 2006 national health interview survey data.
Journal of Manipulative and Physiological Therapeutics, 413-418.
Olin, G., & Rhodes, J. (2005). The five most costly medical conditions, 1997 and 2002:
Estimates for the U.S. civilian noninstitutionalized population. MEPS Statistical brief
#80. Retrieved from
http://www.meps.ahrq.gov/mepsweb/data_files/publications/st80/stat80.pdf O’Toole, T.,
Gibbon, J., Hanusa, B., & Fine, M. (1999). Preferences for sites of care among urban
homeless and housed poor adults. Journal of General Internal
Medicine, 14, 599-605.

102
Ouimete, P., Jemelka, R., Hall, J., Brimner, K., Krupski, A., & Stark, K. (2007). Services
to patients with dual diagnoses: Findings from Washington’s mental health service
system. Substance Use & Misues, 42, 113-127.
Overland, S., Glozier, N., Maeland, J., Aaro, L., & Arnstein, M. (2006). Employment
status and perceived health in the Hordaland Health Study (HUSK). BioMed
Central Public Health, 6, 219. doi:10.1186/1471-2458-6-219
Palinkas, L., Criado, V., Fuentes, D., Shepherd, S., Milian, H., Folsom, D., & Jeste, D.
(2007). Unmet needs for services for older adults with mental illness: Comparison
of views of different stakeholder groups. American Journal of Geriatric
Psychiatry, 16(6), 530-540.
Parabiaghi, A., Bonetto, C., Rugerri, M., Lasalvia, A., & Leese, M. (2006). Severe and
persistent mental illness: A useful definition for prioritizing community-based
mental health service interventions. Social Psychiatry and Psychiatric
Epidemiology, 41, 457-463.
Park, W., & Grindel, C. (2007). Korean American mother and daughter communication
on women’s health topics. Journal of Cultural Diversity, 14(1), 4-11.
Parks, J., Svendsen, D., Singer, P., & Foti, M. (2006). Morbidity and mortality in people
with serious mental illness. National Association of State Mental Health
Program Directors (NASMPD) Medical Directors Council. Retrieved from
http://www.hsmh.state.ut.us/docs/mortality-morbidity_nasmhpd.pdf
Patel, V., & Kleinman, A. (2003). Poverty and common mental disorders in developing
countries. Bulletin of the World Health Organization, 81(8), 609-613.
Perilla, J., Norris, F., & Lavizzo, E. (2002). Ethnicity, culture, and disaster response:
Identifying and explaining ethnic differences in PTSD six months after hurricane

103
Andrew. Journal of Social and Clinical Psychology, 21(1), 20-45.
Philipps, L., Hammock, R. & Blanton, J. (2005). Predictors of self-rated health status
among Texas residents. Preventing Chronic Disease Public Health Research,
Practice and Policy, 2(4), 1-10.
Prevention Institute. (2009). Mental Health. Retrieved from
http://preventioninstitute.org/mental.html
Quill, B. (2001). Reconsidering health disparities. Public Health Reports, 116, 505-514.
Rabin, D., Petterson, S., Basemore, A., Teevan, B., Phillips, R., Dodoo, M., & Xierali, I.
(2009). Decreasing self-perceived health status despite rising health expenditures.
American Family Physician, 1(80), 427.
Rahmqvist, M. (2001). Patient satisfaction in relation to age, health status and other
background factors: a model for comparison of care units. International Society
for Quality in Health Care, 13(5), 385-390.
Ralph-Campbell, K., Pohar, S., Guirguis, L., & Toth, E. (2006). Aboriginal participation
in the DOVE study. Canadian Journal of Public Health, 97(4), 305-309.
Rebhan, D. (2010). Health care utilization: Understanding and applying theories and
models of health care seeking behavior. Case Western Reserve University.
Retrieved from http://www.cwru.edu/med/epidbio/mphp439/healthcareutil.pdf
Rhoades, J. (2004). Research Findings #22: Restricted-activity Days in the United States,
1997 and 2001. Agency for Healthcare Research and Quality, Rockville, MD.
Retrieved from http://www.meps.ahrq.gov/data_files/publications/rf22/rf22.shtml
Richardson, L., & Norris, M. (2010). Access to health and health care: How race and
ethnicity matter. Mount Sinai Journal of Medicine, 77, 166-177.
Rosnow, R., & Rosenthal, R. (2003). Effect sizes for experimenting psychologist.

104
Canadian Journal of Experimental Psychology, 57, 221-237.
Roy-Byrne, P., Joesch, J., Wang, P., & Kessler, R. (2009). Low socioeconomic status and
mental health care use among respondents with anxiety and depression in the
NCS-R. Psychiatric Services, 60(9), 1190-1197.
Rubin, R., Peyrot, M., & Siminerio, L (2006). Health care and patients-reported
outcomes. Diabetes Care, 29(6), 1249-1255.
Sareen, J., Jacobi, F., Cox, B., Belik, S., Clara, I., & Stein, M. (2006). Disability and poor
quality of life associated with comorbid anxiety disorders and physical conditions.
American Medical Association, 166, 2109-2116.
Shaikh, B., & Hatcher, J. (2005). Health seeking behavior and health service utilization in
Pakistan: Challenging the policy makers. Journal of Public Health, 27(1), 49-54.
Sharma, R., Haas, M., & Stano, M. (2003). Patient attitudes, insurance and other
determinants of self-referral to medical and chiropractic physicians. American
Journal of Public Health, 93(12), 2111-2116.
Shepherd, L. (2009). Report shows faults in mental health system. BenefitNews.com.
Health Care, 41. Retrieved from http://ebn.benefitnews.com/news/report-
showsfaults-in-mental-health-system-2672404-1.html
Shimada, H., Lord, S., Yoshida, H., Kim, H., & Suzuki, T. (2007). Predictors of cessation
of regular leisure-time physical activity in community-dwelling elderly people.
Gerontology, 53, 293-297.
Shook, M. (2005). Transportation barriers and health access for patient attending a
community health center. Retrieved from
http://web.pdx.edu/~jdill/Files/Shook_access_transportation_chc.pdf

105
Simonoff, E., Elander, J., Holmshaw, J., Pickles, A., Murray, R., & Rutter, M. (2004).
Predictors of antisocial personality. Continuities from childhood to adult life. The
British Journal of Psychiatry, 184(2), 118-127.
Smith, M., & Bartell, J. (2004). Changes in usual source of care and perceptions of health
care access, quality, and use. Medical Care, 42, 10, 975-984.
Soni, A. (2009). The five most costly conditions, 996-2006: Estimates for the U.S.
civilian noninstitutionalized population. MEPS statistical brief #248. Agency for
Healthcare Research and Quality. Rockville, MD. Retrieved from
http://www.meps.ahrq.gov/mepsweb/data_files/publications/st248/stat248.pdf
Sorkin, D., Tan, A., Hays, R., Mangione, C., & Ngo-Metzger, Q. (2008). Self reported
health status of Vietnamese and non-Hispanic White older adults in California.
Journal of the American Geriatrics Society, 56, 1543-1548.
Stagnitti, M. N. (2009). Trends in outpatient prescription analgesics utilization and
expenditures for the U.S. civilian noninstitutionalized population, 1996 and 2006.
MEPS statistical brief #235. Agency for Healthcare Research and Quality.
Rockville, MD. Retrieved from
http://www.meps.ahrq.gov/mepsweb/data_files/publications/st235/stat235.pdf
Stefanacci, R., & Podrazik, P. (2005). Assisted living facilities: Optimizing outcomes.
Journal of the American Geriatrics Society, 53, 538-540.
Straus, H., Cerulli, C., McNutt, L., Rhodes, K., Conner, K., Kemball, R., Kaslow, N., &
Houry, D. (2009). Intimate partner violence and functional health status:
Associations with severity, danger, and self-advocacy behaviors. Journal of
Women’s Health, 18, 645-631.

106
Studts, C., Stone, R., & Barber, G. (2006). Predictors of access to healthcare services
among groups of TANF recipients in Kentucky. Social Service Review, 80(3),
527-548.
Tam, T., Zlotnick, C., & Bradley, K. (2008). The link between homeless women’s mental
health and service use. Psychiatric Services, 59(9), 1004-1010. Timko, C., Chen, S.
Sempel, J., & Barnett, P. (2006). Dual diagnosis patients in community or
hospital care: One year outcomes and health care utilization and costs. Journal of
Mental Health, 15(2), 163-177.
Trosclair, A., & Dube, S. (2010). Smoking among adults reporting lifetime depression,
anxiety, anxiety with depression, and major depressive episode, United States,
2005-2006. Addictive Behaviors, 365, 438-443.
Tsay, J., Lee, C., Hsu, Y., Wang, P., Bai, Y., Chou, Y., Huang, N. (2008). Disparities in
appendicitis rupture rate among mentally ill patients. BioMed Central Public
Health. Retrieved from http://www.medscape.com/viewarticle/569620_print U.S.
Census Bureau. (2010). Population estimates. Retrieved from
http://factfinder.census.gov/
Vega, W., Kolody, B., & Aguilar-Gaxiola, S. (2001). Help seeking for mental health
problems among Mexican Americans, Journal of Immigrant Health, 3(3), 133-
140.
Von Ah, D., Ebert, S., Ngamvitroj, A., Park, N., & Kang, D. (2004). Predictors of health
behaviors in college students. Issues and Innovations in Nursing Practice, 48(5),
463-474.
Wagner, T., & Guendelman, S. (2000). Healthcare utilization among Hispanics: Findings
from the 1994 minority health survey, The American Journal of Managed Care, 6,
355-364.

107
Waidman, M., & Rajan, S. (2000). Race and ethnic disparities in health care access and
utilization: an examination of state variation. Medical Care and Research Review,
57, 55-84.
Ware, J., Kosinski, M., & Keller, S. (1996). A 12-item short-form health survey:
Construction of scales and preliminary tests of reliability and validity. Medical
Care, 34, 220-233.
Washington, D., Villa, V., Brown, A., Damron-Rodriquez, J., & Harada, N. (2005).
Racial/ethnic variations in Veteran’s ambulatory care use. American Journal of Public
Health, 95(12), 2231-2237.
Weigers, M. E., & Drilea, S. K. (1999) Research findings #10: Health status and
limitations: A comparison of Hispanics, Blacks, and Whites, 1996. Agency for
Healthcare Research and Quality. Rockville, MD. Retrieved from
http://www.meps.ahrq.gov/data_files/publications/rf10/rf10.shtml
Weinick, R.M., Burns, R., & Mahrotra, A. (2010). Many emergency department visits
could be managed at urgent care centers and retail clinics. Health Affairs, 29(9),
1630-1636.
Weinick, R. M., Zuvekas, S. H., & Drilea, S. (2006). Research findings #3: Access to
Health Care - Sources and Barriers, 1996. Agency for Healthcare Research and
Quality. Rockville, MD. Retrieved from
http://www/meps.ahrq.gov/data_files/rtf3.shtml
Wiechelt, S., Delprino, R., & Swarthout, J. (2009). Characteristics of traumatic
experience and survivor perceptions of mental health services: The 2004-2005
Erie county community trauma survey. Journal of Aggression, Maltreatment &
Trauma,18(5), 484-498.

108
Wilper, A., Woolhandler, S. Lasser, K. McCormick, D., Bor, D., & Himmerlstein, D.
(2009). Health insurance and mortality in U.S. adults. American Journal of Public
Health, 99(12), 2289-2295.
Woodward, A., Dwinell, A., & Arons, B. (1992). Barriers to mental health care for
Hispanic Americans: A literature review and discussion. Journal of Mental Health
Administration, 19(3), 224-237.
Wu, C., Erickson, S., & Kennedy, J. (2009). Patient characteristics associated with the
use of antidepressants among people diagnosed with DSM-IV mood disorders:
Results from the National comorbidity survey replication. Current Medical
Research & Opinion, 25(2), 471-482.
Xiao, H., & Barber, J. (2008). The effect of perceived health status on patient satisfaction.
Value in Health, 11(4), 719-725.
Xie, H., McHugo, G., Helmstetter, B., & Drake, R. (2005). Three-year recovery
outcomes for long-term patients with co-occurring schizophrenic and substance
use disorders. Schizophrenia Research, 75, 337-348.
Xu, K. (2002). Usual source of care in preventive service: a regular doctor versus a
regular site. Health Services Research, 37(6), 1509-1529.
Zeber, J., Copeland, L., McCathy, J., Bauer, M., & Kilbourne, A. (2009). Perceived
access to general medical and psychiatric care among Veterans with bipolar
disorder. American Journal of Public Health, 99(4), 720-727.

