


1
Chapter 1: Introduction to the Study
Lead is a naturally occurring toxic metal, and widespread use has resulted in
extensive environmental contamination and public health problems around the world.
According to the World Health Organization (WHO, 2019), in 2016 lead exposure
accounted for 63.2% of the global burden of idiopathic developmental intellectual
disability, 10.3% of hypertensive heart disease, 5.6% of ischemic heart disease, and 6.2%
of stroke. The WHO added that in 2017 lead exposure was associated with 1.06 million
deaths and 24.4 million years of healthy life lost worldwide.
The highest burden of childhood lead exposure has been reported in low- and
middle-income countries. For example, in South Africa, Barnes (2017) reported that over
1,400 deaths in children were associated with lead poisoning annually. In Nigeria, a 2010
outbreak of acute lead poisoning killed more than 400 children under the age of 5 years
and left more than 2,000 children with permanent disabilities (Kaufman et al., 2016). It is
estimated that about 90% of children diagnosed with blood lead reside in developing
countries (Schultz, 2016). Childhood lead poisoning continues to be a public health
problem in industrialized countries as well. For instance, Hauptman et al. (2017) reported
that more than half a million children in the United States had elevated blood lead level
(EBLL) or blood lead level (BLL) above the reference level of 5 micrograms per deciliter
(µg/dL) in 2017.
Lead has no biological role in the body, and any detectable BLL is abnormal
(Mayans, 2019). There is evidence that a BLL as low as 5 µg/dL in children cans cause
many health and developmental problems including decreased intelligence, behavioral

2
difficulties, and learning problems (Delgado et al., 2018; Mayans, 2019). There is also
evidence that as BLL increases, the range of symptoms, severity, and effects on
children’s health also increases. Many researchers have reported that blood lead level as
high as ≥ 70 µg/dL may cause severe neurologic problems including seizures, comas, and
death (American Academy of Pediatrics Council on Environmental Health, 2016;
Raymond & Brown, 2017).
In addition to those health problems, childhood lead poisoning has also been
associated with significant societal financial and economic costs. The Centers for Disease
Control and Prevention (CDC, 2019a) stated that a federal investment of $80 billion
would be needed to prevent all U.S. children born in 2018 from having any detectable
levels of lead in their blood. Major risk factors of childhood lead exposure include lead-
based paint in older houses and lead in drinking water. Evidence suggested that about
70% of childhood lead exposure can be attributed to lead-based paint and the remaining
30% to lead-contaminated drinking water and imported goods such as candies, spices,
pottery, and herbal remedies (Mayans, 2019). Childhood lead exposure has also been
associated with socioeconomic, racial, and ethnic factors. According to the CDC (2019a),
children living at or below the federal poverty level and children living in older housing
are at greater risk of lead exposure, and that being non-Hispanic African American put a
child at greatest risk of lead exposure.
The definition of EBLL for children is not consistent across the United States. A
recent report indicated that 36 states and the District of Columbia use a blood lead
content of ≥ 5 µg/dL as the cutoff for EBLL; four states use a blood lead content of ≥ 10

3
µg/dL as the cutoff, one state uses a blood lead content of ≥ 3µg/dL as the cutoff, and
three states do not specify a cutoff limit. This inconsistency has been observed in certain
cities within different states as well. For example, New York City, New York;
Philadelphia, Pennsylvania; and Marion County, Indiana all use ≥ 5 µg/dL as the cutoff
limit for EBLL while the states of New York, Pennsylvania, and Indiana use ≥ 10 µg/dL
as the cutoff for EBLL (Michel et al., 2020; Robert et al., 2017).
In Chapter 1, I first provide background information about childhood lead
exposure in the United States and Marion County, Indiana. I then state the problem and
the purpose of this study followed by the research questions and hypotheses that were
tested. These sections are followed by the theoretical framework and the nature of the
study. I then provide definitions of important keywords and phrases frequently used in
this study. The definitions section is followed by the assumptions, limitations, and
significance sections of the study. I close this chapter with a summary of the main ideas
discussed.
Background
The need to eliminate lead in the environment and to prevent childhood lead
poisoning in the United States has been recognized as a public health priority since the
early 1970s. This has been evidenced by several federal-level policies including the
Lead-Based Paint Prevention Act of 1971 and the ban of lead-based paint for residential
use in 1978 and plumbing works in 1986. These policies have contributed to a significant
decrease the median childhood BLL in the United States (American Academy of
Pediatrics Council on Environmental Health, 2016). The percentage of children under 6

4
years old who were diagnosed with EBLL fell from 7.6% in 1997 to 0.6% in 2013 (Child
Trends Data Bank, 2015; Raymond & Brown, 2016).
Despite this general decline in childhood lead poisoning indicators at the national
level, childhood lead exposure continues to be a public health issue in many communities
across the United States as evidenced by the 2015 Flint, Michigan water crisis. In Flint,
lead-contaminated public drinking water supply source caused an additional 561 children
with EBLL, with a conservative estimate of social costs of $65 million (Zahran et al.,
2017). Across the United States, a recent report indicated that an annual average of 1,558
emergency department visits were associated with lead exposure and that about 55% of
these emergency department visits involved young people below the age of 18 years
(Hauptman et al., 2017).
Screening for blood lead has been widely accepted as the best approach to prevent
adverse health and developmental effect of lead in children. Starting in 1978, the CDC
recommended universal screening of all children between the ages of 9 months and 6
years (Ettinger, Leonard, & Mason, 2019). However, by 1997 the CDC recognized that
the risk for lead exposure varied by geographic location, and therefore encouraged states
to look at risk patterns and develop targeted screening strategies (Ettinger, Leonard, &
Mason, 2019).
Presently there is a patchwork of childhood lead poisoning prevention and
screening policies across the United States (Dickman, 2017). For example, the Marion
County Public Health Department (MCPHD, n.d.) adopted universal screening for
childhood lead poisoning prevention while the Indiana State Department of Health

5
(ISDH, 2016) recommended targeted screening. The CDC is currently funding childhood
blood lead surveillance in many communities across the United States (Ettinger, Leonard,
& Mason). However, operational activities on the ground are regulated by state and local
statutes (Ettinger, Leonard, & Mason, 2019). In Marion County, Indiana, blood lead
surveillance data reporting, monitoring, and preventive measures are regulated by
Chapter 29 of the 2007 Indiana State Administrative Code (Indiana Administrative Code,
2007).
In terms of reporting, the statute requires that the results of a childhood blood test
be reported to ISDH no later than 1 week after carrying out the test. Also, the rule
requires that the name, address, and telephone number of the person who carried out the
blood test as well as the physician, hospital, or clinic that submitted the blood specimen
be reported to ISDH (Indiana Administrative Code, 2007; ISDH, 2016, 2018). In terms of
case management and follow-up services for children with EBLL, the statute requires the
local health department do the following: (a) notify the child’s primary medical provider
within 10 working days of receipt of test results, (b) provide educational materials to the
parents or family of the child regarding prevention of lead poisoning, and (c) take any
additional actions that may assist the family in preventing the child’s BLL from
increasing (Indiana Administrative Code, 2007; ISDH, 2016, 2018). In terms of
childhood lead exposure prevention, the statute gives guidance on when a local health
officer can inspect a private property to identify potential lead hazards in the property.
Also, the statute provides guidance for the health officer to order reasonable and

6
necessary actions to prevent or to remediate lead hazards in the property (Indiana
Administrative Code, 2007; ISDH, 2016, 2018).
Problem Statement
Risk factors of childhood lead exposure are relatively common in Marion County,
Indiana. According to the U.S. Census Bureau (2019), about 29% of the population in
Marion County is African American; 45% to 65% of the houses were built before 1980,
and about 32% of children under the age of 5 years were below the federal poverty level.
In addition, the 2018 Census Tract Map showed that seven of the 37 zip codes in the
county were high-risk areas when considering childhood lead exposure (MCPHD, n.d.).
In 2018, about 1.10% of children in Marion County, Indiana, had been diagnosed with
EBLL (ISDH, 2018).
Purpose of the Study
In Marion County, Indiana, EBLL occurs when a venous blood test produces a
lead content of ≥ 5 µg/dL, or when two consecutive capillary blood tests within 2 weeks
of each other show a blood lead content of ≥ 5 µg/dL (Indiana Administrative Code,
2007). Children diagnosed with EBLL have been provided with case management and
follow-up services including (a) home inspections by a state-certified lead inspector
following the U.S. Department of Housing and Urban Development (HUD) guidelines;
(b) parents and guardians education such as awareness of potential lead hazards,
symptoms and behaviors when a child is exposed to lead poisoning, and importance of
good nutrition for the prevention and treatment of lead exposure; and (c) referring
children to social programs such as Head Start and Women Infant & Children (WIC)

7
programs for good nutrition and cognitive development (Delgado et al., 2018, Michel et
al., 2020). However, no study had addressed the effectiveness of these services in
bringing children’s BLL below the reference level of 5 µg/dL in Marion County, Indiana.
The purpose of this study was to fill that gap.
Research Questions and Hypotheses
RQ1: Is there a difference between blood lead level at baseline and blood lead
level at post-case-management time?
Ho1: The difference between blood lead level at baseline and blood lead level at
post-case-management time is not statistically significant at alpha = 0.05 probability
level.
Ha1: The difference between blood lead level at baseline and blood lead level at
post-case-management time is statistically significant at alpha = 0.05 probability level.
RQ2: Is there a difference between blood lead level at baseline and blood lead
level at post-case-management time that may be modifiable by race, education, income,
and zip code levels?
Ho2: There is no modification of the difference between blood lead level at
baseline and blood lead level at post-case-management time by race, education, income,
and zip code levels.
Ha2: There is a modification of the difference between blood lead level at baseline
and blood lead level at post-case-management time by race, education, income, and zip
code levels.

8
RQ3: Can the difference between baseline and post-case-management be
modified by the severity of the baseline blood lead level?
Ho3: There is no modification of the difference between blood lead level at
baseline and blood lead level at post-case-management time by the severity of baseline
blood lead level.
Ha3: There is a modification of the difference between blood lead level at baseline
and blood lead level at post-case-management time by the severity of baseline blood lead
level.
Theoretical Framework
The theoretical base of this study was the health belief model (HBM; Glanz et al.,
2008). The HBM posits that people are more likely to take health promotion or risk
prevention action if they believe that they are susceptible to a disease (perceived
susceptibility), if they believe that the disease may cause serious health consequences
(perceived severity), if they believe that taking an action would reduce the susceptibility
or severity or may lead to positive outcomes (perceived benefits), and if they perceive
few negative attributes are associated with that action (perceived barriers; Jones et al.,
2015; Salari & Filus, 2017). In addition to these original four constructs, researchers have
added two other constructs including self-efficacy and cues to action. Self-efficacy is the
belief that a person can complete the behavior of interest despite the perceived barriers
while cues to action include factors in an individual’s environment such as experiencing
the symptoms of the disease (Jones et al., 2015; Salari & Filus, 2017).

9
The HBM has been widely used to explain people’s behaviors and uptakes of
vaccinations and screenings in many health conditions. Fall et al. (2018) found that
perceived susceptibility and benefits were significant independent predictors of
vaccination intention while perceived barriers had a negative tendential effect on the
intention to get a vaccination. In addition, Fall et al. found that perceived self-efficacy
and perceived benefit significantly predicted vaccination behavior 1 year after they
interviewed study subjects.
Parents and guardians of children exposed to EBLL do not see the urgency of lead
screening because there is a delay or absence of symptoms and health effects. HBM
constructs may therefore provide a theoretical framework to understand the thinking of
parents and guardians when they decide to screen their children for lead exposure. Lead
poisoning is often asymptomatic even at higher blood lead levels of 45 μg/dL or greater
(Hauptman et al., 2017; Mayans, 2019). Therefore, this study was conducted to evaluate
parents’ and guardians’ behaviors toward case management and follow-up
recommendations using these constructs. For instance, a high level of parental
compliance to case management and follow-up recommendations may be explained by
the perception that exposure to lead constitutes a substantial threat to their children’s
health and success.
Nature of the Study
This was a quantitative study with a retrospective cohort design using data from
case management and follow-up charts of children exposed to EBLL in Marion County,
Indiana, between January 2018 and December 2019. A convenience sampling technique

10
was used to sample study subjects with the following selection criteria: (a) children of
age 6 or younger, (b) children diagnosed with EBLL, and (c) children enrolled in case
management and follow-up. A paired t test was used to answer Research Question 1
because the measurements of BLLs were carried out on the same individual. Multiple
regressions were used to answer Research Question 2. The analysis of variance
(ANOVA) method was used to answer Research Question 3 (see Daniel & Cross, 2013;
McDonald, 2014).
Definitions
410-IAC-29: Designation of Chapter 29 of the 2007 Indiana Administrative Code
that regulates the reporting, monitoring, and preventive procedures for lead poisoning
(Indiana Administrative Code, 2007).
Blood lead test: Any blood lead draw (capillary, venous, or unknown sample
type) on a child that is analyzed by a CLIA-certified facility or an approved CLIA-
waived portable device and produces a quantifiable result (CDC, 2019b).
Case management: The process of providing, overseeing, and coordinating lead
poisoning services, including but not limited to the following:
• outreach and identification of children with EBLLs
• child case management service planning and resource identification
• child case management service implementation and coordination
• monitoring of child case management service delivery, program advocacy,
and program evaluation (Indiana Administrative Code, 2007).

11
Children at risk: Children who have any or combination of the following
conditions:
• lives in or regularly visits a house or other structure built before 1978
• has a sibling or playmate who has been lead poisoned
• has frequent contact with an adult who works in an industry or has a hobby
that uses lead
• is an immigrant or refugee or has recently lived abroad
• is a member of a minority group
• is a Medicaid recipient
• uses medicines or cosmetics containing lead
• lives in a geographic area that increases the child’s probability of exposure to
lead (Indiana Administrative Code, 2007).
CLIA: A Clinical Laboratory Improvement Amendments (CLIA)-certified facility
(CDC, 2019b).
CLIA waived: A Clinical Laboratory Improvement Amendments (CLIA)-waived
facility (CDC, 2019b).
Confirmed EBLL: A child with one venous blood test ≥ 5 μg/dL or two capillary
blood tests ≥ 5 μg/dL drawn within 2 weeks of each other (Indiana Administrative Code,
2007).
Elevated blood lead level (EBLL): A single blood lead test (capillary or venous) at
or above the reference value of 5 µg/dL (CDC, 2019b; Indiana Administrative Code,
2007).

12
Percentage of children tested: The number of children less than 72 months of age
tested for blood lead divided by the total number of children less than 72 months of age
within a geographic unit (i.e., county or state) based on annual intercensal estimates for
the most recent U.S. Census data, multiplied by 100 (CDC, 2019b).
Percentage of children with EBLLs: The number of children less than 72 months
of age with an elevated blood lead level ≥ 5 µg/dL divided by the number of children less
than 72 months of age tested for blood lead, multiplied by 100 (CDC, 2019b).
Screening test: A blood lead test for a child age < 72 months who previously did
not have a confirmed elevated BLL (CDC, 2019b).
Test type: A blood lead test that may be conducted for screening, confirmation, or
follow-up (CDC, 2019b).
Assumptions
I used secondary data from a CDC-funded childhood lead poisoning prevention
surveillance data set, which was collected by the Healthy Home and Senior Care
Department of the MCPHD. I made the following assumptions. First, I assumed that the
primary data had been collected using valid instruments and by adhering to ethical and
quality standards required by the Indiana Administrative Code 410-IAC-29. Second, I
assumed that parents and guardians who consented to screen their children for lead
exposure behaved in the framework of the HBM constructs including perceived
susceptibility, severity, benefits, and barriers of childhood lead poisoning condition (see
Jones et al., 2015; Salari & Filus, 2017). Finally, I assumed that the data set was
representative of the county population in terms of ethnic, racial, and socioeconomic

13
characteristics. These assumptions were essential for the generalizability of the findings
of this study.
Scope and Limitations of the Study
I analyzed the BLLs of young children between the ages of 0 and 72 months.
Therefore, the findings and interpretations of the results of this study may not apply to the
adult population because the effect of lead in children is different from that in adults (see
Mayans, 2019). Also, this study was designed as a retrospective cohort study; therefore,
selection bias due to loss to follow-up and information bias due to misclassification were
limitations (see Howe et al., 2016). In addition, I used a convenience sampling method
that limited the generalizability of the results (see Jager et al., 2017).
Significance
This study was conducted to determine whether case management is effective in
bringing down the BLL of children diagnosed with EBLL in Marion County, Indiana.
Evidence from this study may be critical for the efficient allocation of scarce resources at
the MCPHD. Such evidence may also be important for establishing effective intervention
plans for subsequent lead surveillance programs in Marion County, Indiana. In addition,
the results of this study may be used to create an educational tool kit for childhood lead
prevention. Finally, the result of this study may effect social change by indicating which
of the management and follow-up services should be considered first when resources are
scarce.

14
Summary
This chapter included an introduction to the global burden of lead exposure. The
introduction indicated that although 90% of childhood lead burden occurs in developing
countries, children in developed countries like the United States continue to be exposed
to lead poisoning as evidenced by half a million U.S. children diagnosed with EBLL in
2017 (Hauptman et al, 2017). In the background section, I discussed some major U.S.
policies that were developed to eliminate lead in the environment and to prevent
childhood lead exposure. Examples of such policies included the federal ban of lead-
based paints and the adoption of universal and targeted screening policies across states
and local jurisdictions (American Academy of Pediatrics Council on Environmental
Health, 2016; Dickman, 2017). The background also addressed the Indiana
Administrative Code 410-IAC-29, which regulates the reporting, case management, and
follow-up services and prevention of childhood lead exposure in Marion County. Also,
the background addressed the research gap that this study was conducted to fill. The
problem statement and the purpose of the study sections addressed risk factors of
childhood lead poisoning and case management services provided to children diagnosed
with EBLL in Marion County, Indiana (Indiana Administrative Code, 2007; ISDH,
2018).
I used the HBM as the theoretical basis for the study. The HBM posits that the
risk of susceptibility, risk of severity, benefits of the action, barriers to action, self-
efficacy, and cues to action drive the probability of an individual to adopt a health
promotion and health risk prevention behavior (Jones et al., 2015). The HBM was an

15
appropriate theoretical framework to understand the thinking of parents and guardians
when they decide to screen their children for lead exposure (see Salari & Filus, 2017).
The nature of the study section addressed the research design and method and the
analytical approach. This was followed by a section that provided definitions of
important keywords and phrases used throughout this study. This chapter ended with
sections that described the assumptions, limitations, and significance of the study,
respectively.

16
Chapter 2: Literature Review
The problem statement of this study included factors associated with childhood
lead exposure, such as risk factors, preventive strategies, EBLL reference limit, follow-
up, and case management. In this chapter, I present a synthesis of previous research about
those factors to provide a context of the importance of this study. Keywords and phrases
used to identify these articles includes childhood lead exposure, childhood lead
poisoning, reference level, elevated blood lead level, case management, follow-up, lead
in drinking water, risk factors, screening, and lead regulations. I used combinations of
these keywords and phrases using “AND” as the connector. The following search engines
were used to search these keywords: Thoreau, Cinahl, Medline, and PubMed. These
search engines were accessed through the Walden University Library website. The
Google search engine was also used to access some of the cited articles. Most of the
articles in this review came from peer-reviewed journals. However, this review also
included reports and data from federal and state agencies including the CDC,
Environmental Protection Agency (EPA), and HUD.
In this review, I first synthesized evidence about the origin, constructs, validity,
and rationale of using the HBM (Harrison et al., 1992; Janz & Becker, 1984; Zimmerman
& Vernberg, 1994) as the theoretical background for this study. I then synthesized
research findings and reports about the properties and utility of lead (EPA, 2020; Wani et
al., 2015), its toxicity (Mayans, 2019; Wani et al., 2015), and its negative effects on
children’s health and academic performance (He et al., 2019; Yeter et al., 2020). Next, I
synthesized the literature on the routes of lead exposure (Carrel et al., 2017; Wani et al.,

17
2015), the sources of lead exposure (Hauptman et al., 2017; Mayans, 2019), and the risk
factors of lead childhood lead exposure (CDC, 2020; Hauptman et al., 2017; HUD, 2011)
successively. After these sections, I synthesized the prevalence of EBLLs in children in
the United States (CDC, 2019a; Hauptman et al., 2017). I then addressed the primary and
secondary strategies to prevent childhood lead exposure in the United States. In the last
section, I addressed the factors affecting the CDC-funded Childhood Lead Poisoning
Prevention Program (CLPPP) in Indiana (CDC, 2020b; ISDH, 2016, 2018).
Theoretical Foundation
Origin and Constructs of the Health Belief Model
I used the HBM (see Janz & Becker, 1984) as the theoretical basis for the study.
The HBM was developed in the early 1950s by U.S. social psychologists in response to
poor uptake of free tuberculosis screening(Janz & Becker, 1984). The model has become
a popular theory to explain preventive health behaviors in various disease conditions
(Glanz et al., 2008; LaMorte, 2019; Sundstrom et al., 2015). The HBM posits that people
are more likely to adopt a disease prevention behavior if they think they are susceptible to
the disease (perceived susceptibility), if they think the disease can cause serious damage
to their health (perceived severity), if they believe that they can achieve a better outcome
by adopting the action (perceived benefits), and if they do not anticipate any negative
consequences related to the health behavior (perceived barriers; Glanz et al., 2008; Janz
& Becker, 1984).
In addition to these four original constructs (perceived susceptibility, perceived
severity, perceived benefits, and perceived barriers), four other constructs including self-

18
efficacy and cues to action were later added to the model (Janz & Becker, 1984;
Sundstrom et al., 2015). Self-efficacy is the belief that a person can complete health
behavior despite the existence of barriers (Glanz et al., 2008; Janz & Becker, 1984). Self-
efficacy was added to the model recently (LaMorte, 2019) and was rarely evaluated in the
mid-1980s (Carpenter, 2010; Jones et al., 2015). Cues to action can be viewed as the
stimuli needed to trigger the decision to adopt healthy behavior. These stimuli are
specific to the health condition, and they can be internal or external to the person such as
disease symptoms and awareness advertisement (LaMorte, 2019; National Cancer
Institute, 2005).
Validity of the Health Belief Model
The validity of the HBM has been evaluated in many reviews and meta-analyses
(Carpenter, 2010; Jones et al., 2015). Janz and Becker (1984) summarized the results of
46 HBM studies that examined various health behaviors including preventive-health
behaviors, sick-role behaviors, and clinic utilization behaviors. Janz and Becker found
that perceived barriers, perceived benefits, and perceived susceptibility are better
predictors of the behavior than perceived severity.
A meta-analysis by Harrison et al. (1992) showed that HBM worked best for
retrospective studies than for prospective studies. This finding suggests that the HBM
may not be very good at predicting future behavior. This meta-analysis also suggested
that perceived benefit and perceived barrier have a bigger effect on behavior than
perceived severity.

19
In another meta-analysis, Zimmerman and Vernberg (1994) examined the ability
of the HBM to predict behavior without regard to the effects of each construct on
behavior. Zimmerman and Vernberg found that the HBM was a weak predictor of
behavior compared to the social cognitive theory and the theory of reasoned action. More
recently, Carpenter (2010) conducted a meta-analysis of HBM to elucidate uncertainty
concerning which HBM construct is most strongly related to health behavior. Carpenter
found that perceived benefits and perceived barriers were consistently the strongest
predictors. Despite these inconsistencies, the HBM continues to be used widely to
explore various health conditions such as breast cancer screening (Conley et al., 2019;
Tapera et al., 2019), vaccination uptake (Fall et al., 2018; Sundstrom et al., 2015), or
diabetes management (Alatawi et al., 2016; Tang et al., 2015).
Use of Health Belief Model in Lead Exposure Studies
Studies that addressed HBM constructs in the contest of childhood lead poisoning
are rare. Anderson et al. (1999) compared the perception of mothers of children
diagnosed with EBLL with the perception of mothers with children without EBLL and
found no statistically significant differences between these groups of mothers. Anderson
et al. attributed the absence of significant differences between these groups to the fact
that EBLL may not have symptoms, and so mothers of children exposed to EBLL do not
perceive the threat of lead exposure, which could have driven them toward preventative
health actions.
Polivka and Gottsman (2005) conducted focus group discussions to assess
parental perceptions of barriers to blood lead testing in the state of Ohio. Polivka and

20
Gottsman found that most parents were not familiar with the causes and effects of lead
poisoning. In addition, most parents wished to do lead testing during their WIC visits to
limit the travel time. This finding suggests that in addition to the lack of perceived threat,
transportation to the lead testing sites may also be a barrier to uptake of lead screening.
The fact that lead exposure is asymptomatic has been supported by many recent
studies. Mayans (2019) reported that lead poisoning is often asymptomatic even at blood
levels as high as 45 μg/dL; a value that is 9 times higher than the current CDC reference
level of 5 μg/dL. Haboush-Deloye et al. (2017) remarked that without signs and
symptoms, parents may not rush lead screening testing.
Rationale for Using the HBM in the Current Study
The rationale for using the HBM for this study derived from two considerations.
First, the data set for this study came from a CDC-funded CLPPP (CDC, 2020c), and the
HBM has been widely used to explain people’s motivation and participation in disease-
prevention screening programs (Conley et al., 2019; Glanz et al., 2008; Tapera et al.,
2019). The HBM was associated with an X-ray screening campaign for the early
detection of tuberculosis in the 1950s (Glanz et al., 2008).
Second, risk factors of childhood lead exposure can be mapped to constructs of
the HBM. For example, it can be hypothesized that living in older lead-based paint
houses would be a perceived susceptibility factor to motivate parents to screen their
children for lead exposure (see Glanz et al., 2008). In addition, it can be assumed that
evidence of loss of academic performance associated with childhood EBLL (see

21
Sorensen et al., 2019) would motivate parents to participate in the CDC-funded CLPPP
as a perceived susceptibility factor (see Glanz et al., 2008).
Properties and Utility of Lead
Lead can be described as a bluish-white metal, which when freshly cut shows a
bright luster but tarnishes when exposed to air (Abadin et al., 2007). Lead has many
physical properties that make it attractive for industrial use. Lead is very soft, highly
malleable, and ductile. In addition, lead is a poor conductor of electricity and is very
resistant to corrosion (Abadin et al., 2007; Wani, et al., 2015). These proprieties probably
explain why lead was extensively used in plumbing during the Roman era. It worth
noting that the word plumbing is derived from the Latin name of lead (Delile et al., 2017;
Robin, 2008).
Lead also has properties that may explain its attractiveness to the paint industry.
Lead makes the paint more durable and improves its adherence to surfaces. Lead
compounds also allow the making of various paint colors such as the use of lead
carbonate to make white paint and the use of lead chromate to make yellow paint
(O’Connor et al., 2018). Today, the lead acid battery industry is the principal user of lead
accounting for more than 85% of U.S. lead consumption in 2018 (Abadin et al., 2007).
However, despite the enactment of many regulations to curb the presence of lead in the
environment, lead-containing products are still ubiquitous in modern industrial and
household items including paint, ceramics, pipes and plumbing materials, solders,
gasoline, batteries, ammunition, and cosmetics (EPA, 2020).

22
Problems of Lead Exposure
Lead Toxicology
Lead has no physiologic value in the body, and its adverse impact on human
health has been recognized since at least the second century BC (Delile et al., 2017).
Much of lead’s toxicity has been associated with distortion of the cell membrane, DNA,
enzymes, and structural proteins (Wani et al., 2015). Lead also interferes with the
synthesis of essential biomolecules such as Vitamin D and hemoglobin. Specifically, lead
interferes with enzymes such as D-aminolevulinate dehydratase and ferrochelatase, which
are essential for the synthesis of the heme ring (Wani et al, 2015), and this may explain
the association between lead poisoning and anemia (Hauptman et al., 2017).
Many of lead’s toxic properties are also due to its ability to mimic or compete
with calcium. Lead is a divalent cation, and it can bind strongly to sulfhydryl groups of
protein molecules (Wani et al., 2015). Also, because of its ability to successfully compete
with calcium, lead can negatively affect neuronal signaling in the brain, and this is the
most concerning aspect of childhood lead exposure (Mayans, 2019; Wani et al., 2015).
Lead is also associated with a condition called gingival lead line or Burton line.
Gingival lead line is a blue-purplish line on the gums seen in lead-poisoned individuals,
which is caused by a reaction between circulating lead with sulfur ions released by oral
bacterial activity. As a result of this reaction, lead sulfide compounds deposit at the
junction of the teeth and gums (Babu et al., 2012; Pearce, 2007).

23
Effects of Lead Exposure on Children’s Health and Academic Performance
Several studies have provided evidence that lead has wide-ranging health and
developmental effects on young children. He et al. (2019) reported that lead levels as low
as below 3 µg/dL in children’s bloodstream can affect their brain’s ability to control
impulses and process information. Yeter et al. (2020) added that beginning at a blood
lead content of 2 µg/dL, there is a loss of 1.88 IQ points for each doubling of blood lead
level.
The effect of lead on children’s school performance has also been documented. A
longitudinal study of New Zealand children revealed that elevated lead levels were
associated with poorer reading cores, failure to graduate from high school, and poorer
examination scores (Needleman, 2004; Reuben et al., 2017). Recently Sorensen et al.
(2019) studied the effect of lead hazard control programs on children’s blood lead levels
and students’ test scores. Sorensen et al. found that children’s math and reading scores
increased for every 1 percentage point reduction in children’s blood lead level, and years
later average math test scores improved by 0.03 to 0.04 standard deviations while average
reading scores improved 0.06 to 0.08 standard deviations.
The impact of lead exposure is not limited to the immediate health outcome on
children because the impact of lead exposure can be irreversible, long-lasting, and
affecting children’s future workplace performance and future earning (Reuben et al.,
2017; Mayan, 2019). The societal cost of lead-poisoned children can also be huge
because of the cost of special education. In that perspective, the American Academic of
Pediatrics reported that despite the historical reductions in blood lead concentrations, it

24
has been estimated that the annual cost of childhood lead exposure in the United States is
$50 billion (Council on Environmental Health, 2017).
Route of Lead Exposure
Human exposure to lead can occur through many routes but inhalation, ingestion,
and trans-placental are reported as the most common routes. Wani et al., (2015) reported
that in adults, up to 40% of inhaled lead dust is deposited in the lungs and about 95%
goes into the bloodstream and for ingested inorganic lead, about 15% is absorbed in the
bloodstream. These absorption rates are generally higher in children, pregnant women,
and people with deficiencies of calcium, zinc, or iron (Carrel et al., 2017; Wani et al.,
2015). Besides, the rate of absorption of lead in other body organs such as bones and
teeth appear to be affected by age as well. In adults, the combined rate of lead absorption
in bones and teeth can reach 94%, while in children this rate was estimated to about 70%
(Wani et al., 2015).
The relatively lower lead absorption in children’s bones and teeth suggests that
soft tissues such as the brain, liver, spleen, lungs, or kidneys would absorb more lead and
that may explain lead in children has far greater health and developmental consequences
than in adult (He et al., 2019; Yeter et al., 2020). Besides, according to Wani et al. (2015)
children have rapidly developed and remodeling bones and this allows the lead to be
continuously reintroduced into the bloodstream.
Lead is also known to readily cross the placenta of the developing fetus and
impairs the function of multiple developing organ systems. Multiple studies have shown

25
that lead in the maternal bone can move into the bloodstream, representing therefore an
endogenous source of fetal lead exposure (Carrel et al 2017; Silver, et al., 2016).
According to Carrel et al. (2017), the endogenous lead exposure phenomenon
typically occurs when physiologic stress of pregnancy stimulates mobilization of lead
from bone into maternal blood as a consequence of high calcium demands. Carrel et al.
(2017) added that any or combination of the following factors include high maternal
blood pressure, low calcium levels and milk intake, low hemoglobin levels, and anemia,
and alcohol intake in the third trimester of pregnancy may increase the transfer of lead to
the fetus.
Sources of Lead Exposure
The source of childhood blood lead is diverse. Hauptman et al. (2017) reported
that lead-laden dust and paint chips from deteriorating lead paint on interior building
surfaces constitute the major source of lead found in children diagnosed with EBLL.
Mayan (2019) added that up to 70% of EBLL in children come from a combination of
lead-based paint, lead-laden house dust, and lead-contaminated soil and that the
remaining 30% come primarily from contaminated drinking water and imported goods
such as candies, spices, pottery, and herbal remedies.
Evidence of drinking water as a source of childhood lead exposure is well
documented in the US following the 2014 Flint, MI. water crisis events (Zahran,
McElmurry, & Sadler, 2017). Evidence of imported goods as sources of lead exposure is
also supported by many reports. In 2015 a local health department in the state of
Wisconsin identified an adult with 85.8μg/dL blood lead level. Upon investigation, the

26
source of this exposure was linked to Ayurvedic medications imported from India
(Meiman et al., 2015). More recently, a 12-year-old recent immigrant from Thailand and
two of his younger siblings were diagnosed with EBLL in the state of Georgia, in 2018
and the sources of these exposures were linked to imported tobacco products (El Zahran
et al., 2018).
Another source of childhood lead exposure is “take-home” lead from adults
working in industries such as painting, building renovation, demolition, shooting range,
metal scrap cutting, plumbing, and recycling (Hauptman et al., 2017). In June 2010, a
one-year-old boy and a two-year-old girl were diagnosed with EBLL with 18μg/dL and
14μg/dL, respectively in the state of Ohio. Subsequent investigations linked the sources
of these exposures to the father of the children who has been working in a scrap factory
without protective equipment at work (Newman et al., 2015).
Risk Factors of Lead Exposure
Housing Conditions
It is now widely accepted that children most at risk of lead exposure are those
living in houses built before 1978. The EPA estimates that more than 80% of all homes
built in the U.S. before 1978 contain lead-based paint (HUD, 2011; Yeter et al., 2020),
and there is a significant amount of those houses in the US. For example, a 2011
American Healthy Homes Survey revealed that about 34.9% of all US homes have lead-
based paint; about 21.9% of all homes have one or more lead-based paint hazards and
that an estimated 3.6 million homes with lead-based paint have children below the age of
6 years (Hauptman et al., 2017; HUD, 2011).

27
The average age of housing in a community can therefore provide an indication
of the extent of childhood lead exposure risk factors in a community. According to HUD
(2011), the highest prevalence of lead-based paint housing is found in the Northeast and
Midwest. However, Roberts et al. (2017) analyzed EBLL data from 1999 to 2010 and
found that the greatest number of children with higher than 10μg/dL of blood lead
content resides in the South.
In Indiana, a 2018 report of the State Department of Health indicated that about
60% of all housing was built before 1980, the year considered as the cutoff for lead-based
paint housing stock. This report also indicated that the stock of older housing in Marion
County, IN. was even higher, reaching 65% with potential suggesting a higher risk for
children in that county (ISDH 2018, 2015, 216).
Drinking Water Source
Another risk factor for childhood lead exposure is lead-containing water, either
through service line or poor anti-corrosion control system as evidenced by the 2014 Flint,
MI. water crisis (Zahran et al., 2017). However, it is important to indicate that homes
without lead service lines may still have brass or chrome-plated brass faucets, galvanized
iron pipes, or other plumbing soldered with lead. Infants who drink formula prepared
with lead-contaminated tap water may be at a higher risk of exposure because of the large
volume of water they consume relative to their body size (CDC, 2020; Hauptman et al.,
2017).

28
Socioeconomic Conditions
Risk factors of childhood lead exposure have also been associated with
socioeconomic, racial, and ethnic factors. Children living at or below the federal poverty
level are at higher of lead exposure because they are more likely to reside in older, poorly
maintained housing with lead paint and lead-containing plumbing (CDC, 2019a;
Hauptman et al., 2017).
In terms of racial, ethnic, and socioeconomic status, it is widely accepted that
Blacks and Hispanics are most at risk of childhood lead exposure. Immigrant or refugee
status is a risk factor since children born abroad or whose parents were born abroad may
be more likely to use imported goods that contain elevated levels of lead (Hauptman et
al., 2017). Lower socioeconomic status may also imply imbalanced nutrition such as iron
deficiency. Iron deficiency has been associated with a five-fold increase in the risk of
lead toxicity from the baseline value (CDC, 2019a; Hauptman et al., 2017).
Age is a risk factor because lead absorption, mobility, and behavior are
significantly modified by age. Infant and young children are known to have higher hand-
to-mouth activity, and this puts them at much higher risk of lead exposure than adults
(Mayan, 2019; Wani, et al., 2015). Besides, younger children absorb lead more readily
than older children and adults as evidenced by an analysis of 2009-2010 NHANES
survey data which showed that the median blood lead levels for one-to-two-year age-old
children is much higher (1.2 μg/dL) than that of six to ten years old children (0.8 μg/dL)
(AAP-CEH, 2016).

29
Prevalence of Elevated Blood Lead Level in Children
Childhood blood level has been declining over the past four decades in the US.
Before between 1976 and 1980 the reference value of EBLL was 105 µg/dL and the
prevalence of EBLL was over 80%. Between 1988 and 1991 the prevalence level
dropped to less than 10% (AAP-CEH, 2016). Considering the reference level of ≥5
μg/dL, the prevalence level of EBLL dropped significantly from about 2.6% in 2010 to
about 2.5% in 2017 (Hauptman, et al., 2017).
It is important to indicate that the prevalence of childhood lead exposure is linked
to the current reference value 5 μg/dL which was derived from the 97.5th percentile of the
blood level distribution among children between the ages of one and five years old in the
2007 to 2010 National Health and Nutrition Examination Survey (NHANES) data
(Caldwell, et al., 2017; Mayan, 2019).
In 2012, the CDC adopted this reference value and planned to update it every
four years but has not done so yet. Consequently, the prevalence of EBLL may be higher
if the new NHANES data produces a lower reference value (Mayan, 2019). Caldwell, et
al., (2017) used the 2011 to 2014 NHANES survey data, found the 97.5th percentile
corresponded to 3.48 µg/dL (95% CI, 2.65–4.29 µg/dL) which is about 30% lower than
the current reference value of 5 µg/dL.
There is also evidence that the use of NHANES survey data may underestimate
the lead exposure prevalence in some urban schools. McLaine et al. (2013) reported that
20% and 67% of kindergarteners in a public school in the state of Iowa had least one
BLL ≥10 µg/dL and one BLL ≥5 µg/dL, respectively

30
Lead Exposure Prevention Strategies
Primary Prevention
Primary prevention is the most effective way to protect children against the
harmful effect of lead exposure. Because no safe blood lead level exists, successful
primary prevention should remove every lead hazard from areas where children spend a
significant amount of their time. These areas may home, school facilities, daycares
centers, and playgrounds (Christensen et al., 2019; Ettinger et al., 2019).
Environmental health regulations have been the cornerstone of lead exposure
prevention in the US (Health Impact Project. 2016; Kennedy et al., 2017, 2014). The first
major legislation to remove lead in the environment is the 1971 Lead-Based Paint
Poisoning Prevention Act which banned lead-based paint in the US. Then in 1973, the US
started phasing out lead in gasoline, and in 1978 the US banned lead in residential paint
(Council on Environmental Health, 2017; Health Impact Project, 2017).
In 1992, the Residential Lead-Based Paint Hazard Reduction Act or Title X was
enacted, and in 1995 the US Housing and Urban Development [HUD] established
guidelines for evaluating and controlling residential lead-based paint hazards. In 1999
created the Lead Safe Housing Rule, which was updated in 2012 with new requirements
for lead-based paint notification, evaluation, and remediation (Council on Environmental
Health, 2017; Health Impact Project, 2017).
In 2016, following events in Flint, MI, a renewed focus on identifying and
removing lead from the environment led to the passage of the Water Infrastructure
Improvements for the Nation (WIIN) Act (Ettinger et al., 2019). In 2017, the EPA

31
finalized an amendment to the Lead Renovation, Repair, and Painting Program (RRP)
Rule. The RRP requires that people engaged in Renovation, Repair, and Painting
activities on facilities built before 1978 to be trained and certified in lead-safe work
practices because these repair and renovation activities can create hazardous lead dust
when surfaces with lead paint are disturbed. This rule is therefore created to protect from
lead exposure (Council on Environmental Health, 2017; EPA, 2017; Health Impact
Project, 2017).
Besides, the Occupational Safety and Health Administration (OSHA), has
established standards to prevent workplace lead exposure for general industry, shipyards,
and construction employers. These standards set also set an action level of 30 micrograms
per cubic meter (μg/m3) at which an employer must begin specific compliance activities
such as blood lead testing for exposed workers (US Department of Labor, n.d.).
OSHA often uses the national Adults Blood Lead Epidemiology and Surveillance
(ABLES) data to identify industries whose employees exhibit high BLLs (Alacron,
2016). In February 2016, an OSHA enforcement investigation found that shipyard
workers in Superior, Wisconsin, were exposed at ≥20 times the permissible exposure
limit (Egan, Tsai, & Chuke, 2019).
Regulations to prevent childhood lead exposure were expanded to other potential
sources as well. The 2008 Safe Drinking Water Act allows the EPA to establish a
treatment technique that prevents lead and copper from getting in the drinking water. In
addition, the Lead-Free Toy Act allowed the Consumer Protection Safety Committee to

32
set a limit on the lead content of toys (Council on Environmental Health, 2017; Health
Impact Project, 2017).
Other federal agencies have also been actively involved in the prevention of
childhood lead exposure. For instance, since 1998 the Centers for Medicare & Medicaid
Services (CMS) required universal blood lead screening for children receiving program
benefits (Ettinger et al., 2019). In 1995, the Council of State and Territorial
Epidemiologists (CSTE) designated EBLLs as the first noninfectious condition to be
voluntarily “notifiable” at the national level. Consequently, the CDC is now requiring
elevated blood lead levels in the National Notifiable Diseases Surveillance System (Egan,
Tsai, & Chuke, 2019).
It is widely that accepted these regulations and environmental health policies have
made a significant improvement in the prevention of childhood lead exposure. Tsoi et al.
(2016) analyzed blood levels among US children and found that the average blood lead
level in children has declined by about 94%, from 15 µg/dL in 1976, to 0.86 µg/dL in
2014. Also, Kennedy et al. (2014) compared childhood lead prevention data from states
of Massachusetts (MA) and Ohio (HO) which have enacted childhood lead prevention
laws, and Mississippi (MS) which did not have lead exposure prevention. They found
significant differences between lead law states (MA & OH) and the control state (MS) in
terms of number of confirmed cases of lead poisoning at a given address. They also
reported that the states with lead laws were 79% less likely than the ones without
legislation to have residential addresses with subsequent lead poisoning cases among
children younger than 72 months.

33
Despite the success of these regulations and policies in preventing or mitigating
the effect of childhood lead exposure (Kennedy et al., 2016, Kennedy et al., 2014), an
estimated 2.5% of US children between one and five years old are still being exposed to
the effect of EBLL. Besides, this estimate does not include other groups at risk such as
younger or older children pregnant and lactating women, or workers exposed on the job
(Ettinger et al., 2019).
The persistence of lead in the environment in the US may be the consequence of
US reluctance to join the internal community to control lead in the environment.
According to the Health Impact Project (2017), many European countries including
France, Belgium, and Austria banned white-lead interior paint as early as 1909. Besides,
the Health Impact Project (2017) also reported that the US declined to adopt the
International Labor Organization proposal that prohibits the use of lead-based paint in all
member countries in 1921.
Secondary Prevention
A central tenet of secondary prevention is to identify asymptomatic children with
lead in their blood. This should allow the identification and removal of the lead hazard,
and the treatment of contaminated children (Christensen, et al., 2019; Mayan, 2019).
Much of the guidance and recommendations of childhood lead prevention in the
US come from the CDC (Ettinger et al., 2019a; Mayan, 2019). However, the CDC has
been frequently updated its guidance and recommendations to consider new evidence
about childhood lead exposure risk factors and health effect. Thus, in 1975 the CDC

34
recommended screening only children who lived in or visited homes built before 1960
(Ettinger et al., 2019, Yeter et al., 2020).
In 1985, the CDC updated these recommendations to include that all children
should be screened, but priority is should be given to those with one or combination of
the following risk factors: a) living in the older, dilapidated housing, b) living near
heavily trafficked highways, c) being siblings, housemates, visitors, or playmates of
children with known lead toxicity or d) family members had occupational lead exposures.
By 1991, the CDC recommended screening for all children between the ages of one and
five (Ettinger et al., 2019, Yeter et al., 2020).
Presently, the CDC recommends that state and local health departments to
development screening plans that are adapted to their local conditions, and this have led
to a patchwork of screening pattern across the US, with some state and local health
departments adopt universal screening while other applied targeted screening (Dickman,
2017; Michel et al., 2020).
Universal Screening
Universal screening is regarded as the most effective approach to secondary
prevention of childhood lead exposure (Dickman, 2017; Yeter et al., 2020). Thus, since
1998, the Centers for Medicare & Medicaid Services (CMS) require universal screening
for all children receiving program benefits (Ettinger et al., 2019, Yeter et al., 2020). As of
2018, at least 14 states and the District of Columbia presently require universal screening
of children for lead exposure (Dickman, 2017; Michel et al., 2020). In addition, some

35
local health departments such as the city of Philadelphia, PA., and Marion County, IN.,
and East Chicago, IN. also require universal screening (Michel et al., 2020; ISDH, 2016).
Besides, some organizations such as the Pediatric Environmental Health Specialty
Unit (PEHSU) and the American Academy of Pediatrics (AAP) also require universal
screening of children for lead exposure (Michel et al., 2020). The AAP however,
recommends universal screening for children with certain conditions, such as those living
in communities with more than 27% of housing built before 1950 or where the
prevalence of EBLL (≥ 10 µg/dL) for children between the ages 12 and 36 months is ≥
12% (Council on Environmental Health, 2017).
Targeted Screening
Presently, at least 18 health departments in the US are using a targeted approach
to childhood lead exposure screening (Dickman, 2017; Michel et al., 2020). A major
limitation of the targeted approach to childhood lead screening is the challenge of
defining the target criteria that can successfully identify all of the children at risk. This
consideration may make targeted screening less effective compare with the universal
screening approach (Dickman, 2017; Michel et al., 2020).
If targeted screening should be used, the American Academy of Pediatrics (AAP)
recommends screening children of 12 to 24 months old and living in areas where more
than 25% of housing is built before 1960 (Yeter et al., 2020). Screening based on location
could however result in under testing of children in a community. As an example, a local
health department may recommend screening children based on the zip code of residence

36
of children while another health department may recommend testing based on the
location of children’s primary care physician’s practice (Dickman, 2017).
Clinical Diagnosis and Treatment of Lead Exposure
Medical providers play a crucial role in the prevention and early detection of
childhood lead exposure. Mayan (2019) that symptomatic lead poisoning should be an
emergency with immediate hospitalization. The problem is that lead poisoning may not
have specific symptoms and therefore a variety of symptoms and signs can be the result
of lead poisoning (Haboush-Deloye et al., 2017, Mayan, 2019).
Hampton et al. (2017) suggested that “children who present to the emergency
department with the following including persistent gastrointestinal symptoms (e.g.
constipation, abdominal pain, vomiting), unexplained weight loss, unexplained
neurological symptoms (e.g. headaches, fatigue), or behavioral changes (e.g., withdrawn,
confusion, irritability, hyperactivity) or whose skin has a distinct pallor from severe
anemia, should be suspected of suffering from acute lead poisoning” (Clinical Diagnosis
section). In terms of treatment, the CDC recommends chelation therapy only when the
blood lead level is ≥ 45μg/dL. For lower blood lead levels, the CDC recommends prompt
case management and environmental investigations to identify and remove the source of
exposure, despite evidence that the lead levels below 5μg/dL have been associated with
irreversible impaired neurocognitive and behavioral development (Mayan, 2019; Reuben
et al., 2017).
Presently, states use different definitions of EBLL, recommendations for
screening, reporting, follow-up, and case management (Mayan, 2019; Michael et al.,

37
2020). Even the existing CDC recommendations are not being followed by all states and
by every health provider. For example, Michael et al. (2020) observed that only 37 states
use the CDC definition of EBLL. Besides, Haboush-Deloye et al. (2017) reported that in
Clark County, Nevada, only 52% of medical doctors involved in pediatric lead screening
admitted to adhering to CDC BLL testing guidelines. According to Michael et al. (2020),
the lack of a uniform sharable clinical decision system is a challenge to effective pediatric
childhood lead screening and management.
Childhood Lead Poisoning Prevention Program
Since the early 1990s, the CDC has been funding a Childhood Lead Poisoning
Prevention Program (CLPPP) across the US. Today, more than 60 states and local health
departments, are participating in this program (CDC, 2020b). CLPPP aims to eliminate
childhood lead exposure as a public health problem, through strengthening blood lead
screening, surveillance, follow-up, and case management (CDC, 2020b). The CDC
provides guidance and recommendation for the activities of the CLPPP, but most
operational activities of the program at each participating health department are regulated
by the state laws and regulations (Raymond & Mary, 2017).
CLPPP in Indiana
CLPPP activities across the state of Indiana are regulated by Article 29 of the
Indiana Administrative Code (410-IAC-29) which mandates much of the screening, data
reporting, case definitions, follow-up, and case management services (ISDH, 2016,
2018). In particular, 410-IAC-29 mandates that a child becomes a confirmed case of
EBLL and qualify for case management when the result of a blood lead test, taken from a

38
single venous blood test sample or two consecutive capillary blood samples, is ≥10μg/dl
(ISDH, 2016, 2018).
However, in 2015 ISDH’s Lead and Healthy Homes Program (LHHP) started
recommending that case management be provided to children with blood lead level
≥5μg/dL (ISDH, 2016). Thus, the majority of local health departments in the state of
Indiana use blood lead value ≥10μg/dL as a reference value for EBLL. However, some
jurisdictions such as the city of East Chicago and MCPHD do use ≥5μg/dL as a reference
value for EBLL (ISDH, 2016, 2018).
Blood lead testing is most often conducted by family physicians and pediatricians,
either in-office or through a referral to a testing laboratory (ISDH, 2016, 2018). However,
local health departments clinic also routinely provides lead screening (ISDH, 2016,
2018). Organizations like the Indiana Women, Infants, and Children (WIC) program and
Head Start also provide lead screening services (ISDH, 2016, 2018).
The number of children who received blood lead screening in Indiana has been
increasing from 40,811 in 2014 to 68,868 in 2018, suggesting a 69% increase. Similarly,
the prevalence of EBLL (≥10μg/dL) at the state level has increased, from about 0.25% in
2014 to about 0.4% in 2017. The prevalence has however dropped to 0.3% in 2018
(ISDH, 2018).
The rate of childhood lead screening is significantly low in Indiana when
considering CDC and CMS requirements (ISDH, 2018). For example, Medicaid-insured
children are required to receive a blood lead test at 12 and 24 months of age, or as soon as
possible before age 6 (ISDH, 2018; ISDH, 2016). But in 2018, only 21% of Medicaid-

39
insured Indiana’s children between the ages of one and two had been screened,
suggesting that up to 79% of Medicaid-insured children eligible for screening did not get
tested for childhood lead exposure (ISDH, 2018).
Summary and Conclusions
In this chapter, I reviewed the literature about childhood lead exposure. In the first
section, I synthetized research findings of the HBM (Janz & Becker, 1984) as the
theoretical background for this study. While the HBM was created to explain the poor
uptake of free tuberculosis screening in the 1950s, it has since become a popular theory to
help explaining preventive health behaviors in various disease conditions (Glanz et al.,
2008; LaMorte, 2019; Sundstrom et al., 2015). The rationale for using HBM for this
study was also explained in this section. First, because this study uses secondary
screening data, and second because HBM constructs such as perceived susceptibility and
perceived severity (Janz & Becker, 1984; Glanz et al., 2008 ) can be mapped respectively
a) to childhood lead exposure risk factors such as living in older houses (Hauptman et al.,
2017; HUD, 2011), b) and the to the negative effect of lead exposure on children’s
academic performance (He et al., 2019; Yeter et al., 2020).
In the second section, I described the physical and chemical properties that make
lead attractive to many industries. Lead has low electrical conductivity, high malleability,
and is highly resistant to corrosion (Wani et al., 2015). Despite heavy regulations, lead
continues to be ubiquitous in US household and consumer products (EPA, 2020).
The human health problems associated with lead exposure were addressed in the
fourth section of this chapter. Evidence of lead toxicity is well documented with much of

40
the toxicity associated with distortion of the cell membrane, DNA, enzymes, and other
structural proteins due to its ability to mimic or compete with calcium (Wani et al., 2015).
The effect of lead on children is however most concerning because lead affects children’s
brain development (Sorensen et al., 2019; Reuben et al., 2017), their academic
performance (He et al., 2019; Reuben et al., 2017 and their future earnings (Mayan, 2019,
Council on Environmental Health, 2017).
The routes of exposure section show that ingestion and inhalation are the two
most common ways lead get into the body (Carrel et al., 2017; Wani et al., 2015; Yeter et
al., 2020). This section also showed that children are most at risk of lead exposure
because they have rapidly developing and remodeling bones and this allows the lead to be
continuously reintroduced into the bloodstream (Wani et al., 2015; Yeter et al., 2020).
The source of lead exposure section shows that children can be exposed to lead
from a variety of sources (Mayan, 2019), but the most widely cited including, lead paint
on the interior on older building surfaces (Hauptman et al., 2017; Mayan, 2019).
However, other sources such as lead from drinking water (Zahran et al., 2017), imported
goods Newman, et al., 2015) and take-home lead from parents working in lead associated
industries (El-Zahran et al., 2018, Newman et al., 2015) are often cited as well.
The lead risk factors section also indicates the existence of many risk factors for
childhood lead exposure including the age of the house (HUD, 2011; Yeter et al., 2020)
socioeconomic status of children (CDC, 2019a; Hauptman et al., 2017), as well as being
immigrant or refugee (Hauptman et al., 2017).

41
In term of prevalence, the consensus is that the number of children
exposed to in the US has been decreasing since but there is still about half a million
children that are present with elevated blood level (AAP-CEH, 2016; Caldwell et al.,
2017; Hauptman et al., 2017; Mayan, 2019). Besides estimation of the prevalence of
EBLL in children depends on the reference level which has been changing at the national
and state levels. This variation between states is cited as a limitation to an accurate
national prevalence value of childhood lead exposure (AAP-CEH, 2016; Caldwell et al.,
2017; Hauptman et al., 2017; Mayan, 2019).
The section on childhood lead exposure prevention shows two main
strategies including one, primary prevention through environmental regulation and
policies, and two, secondary prevention through blood lead screening and surveillance
(Health Impact Project, 2017; Christensen et al., 2019). Since the early 1970s agencies
such as EPA and HUD have enacted laws and policies that were widely accepted to have
significantly reduced the prevalence level of childhood lead exposure in the US (Health
Impact Project, 2017; Kennedy et al., 2027, 2014). Besides, the CDC has been providing
guidance and recommendation about to best to screen children for lead exposure and
what type of follow-up to provide to children diagnosed with EBLL (Christensen et al.,
2019; Ettinger et al., 2019a; Mayan, 2019).
The CDC also funds a national childhood prevention program called CLPPP
(CDC, 2020b). Thus, more than 60 states and local health departments, including the
state of Indiana and Marion County public health department are partnering with the

42
CDC to prevent childhood lead exposure (CDC, 2020b), though operational activities of
the CLPPP are mostly regulated by state laws (Raymond & Mary, 2017).

43
Chapter 3: Research Method
This chapter includes a description of the research design, methodology, and
strategy for handling internal and external validity threats as well as the ethical
considerations of the study. The research design states the nature of the study and
addresses how the research questions were connected to the design. The methodology
provides information to enable replication of the study. The following topics are
addressed in the methodology: study population, data source, sampling criteria, rationale
for using sampling criteria, variables, and data analysis plan.
The dataset for this study came from the CLPPP, a CDC-funded nationally
recognized program (CDC, 2020). CLPPP has been used in many national and state
reports to describe the prevalence of childhood lead exposure (Ettinger, Leonard, &
Mason, 2019, 2019; ISDH, 2018). The findings of the current study may be compared to
previous reports about childhood lead exposure in the United States.
The ethical dimension of this study hinged on the fact that the study population
included young children. Children are widely recognized as a vulnerable population
because they are not competent to assign informed consent (Bagattini, 2019). For the
current study, ethical considerations included parental consents and privacy. Strategies to
ensure a higher level of ethical standards were discussed. These strategies included
submitting the research documents to the institutional review board (IRB) of the MCPHD
and Walden University.

44
Research Design
This was a quantitative study with a retrospective cohort design. The data set for
this study was extracted from records of the CDC-funded CLPP conducted in Marion
County, Indiana, in 2018 and 2019. I applied a secondary analysis approach to case
management and follow-up records of children diagnosed with EBLL in Marion County,
Indiana, between January 2018 and December 2019 (see ISDH, 2017, 2018). The
objective of the study was to answer the following research questions:
1. Is there a difference between blood lead level at baseline and blood lead level
at post-case-management time?
2. Is there a difference between blood lead level at baseline and blood lead level
at post-case-management time that may be modifiable by parental race,
education, income, and zip code levels?
3. Can the difference between baseline and post-case-management be modified
by the severity of the baseline blood lead level?
Methodology
Study Population
According to Frankfort-Nachmias and Nachmias (2008), content, context, and
time frame of the study population should be stated to describe the study population. The
target population for the current study included children in Marion County, Indiana, who
were diagnosed with EBLL during the CDC-funded CLPPP and who were enrolled in
case management and follow-up program. A major characteristic of this population was
that they were considered the children at risk of lead exposure (Indiana Administrative

45
Code, 2007). The size of this population varied depending on the choice of the reference
value. For example, in 2016 when the reference value was ≥ 5 µg/dL, the total number of
children with EBLL in Marion County Indiana was 307, but in 2018 the reference value
was ≥ 10 µg/dL and the number of children with EBLL dropped to 83 (ISDH, 2016,
2018). Presently the statute that regulates childhood lead poisoning prevention programs
in Indiana mandates that case management and follow-up services start at BLL ≥ 5 µg/dL
(ISDH, 2016, 2018). Therefore, I used a BLL of ≥ 5 µg/dL as a reference value for
EBLL.
Data Source
The data for this study consisted of children’s blood lead test results collected in
Marion County, Indiana, from January 1, 2018, to December 31, 2019. By regulation, all
testing laboratories were to report their blood test results to the ISDH within 1 week
(Indiana Administrative Code, 2007). ISDH maintains these test results in a database that
is only accessible by authorized users to maintain the quality, integrity, security, and
safety of the records. For the current study, the data were accessible through the MCPHD
IRB process.
Sampling Criteria
I used a convenience sampling method with the following criteria: (a) children
with confirmed EBLL, (b) children age 6 or younger, and (c) children whose case
management and follow-up had been completed.

46
Rationale for the Sampling Method
Convenience sampling is appropriate in situations where data are collected from
individuals in easily accessible locations such as schools and clinics. These locations are
routinely visited to collect data on individuals as part of program implementation (Hedt
& Pagano 2011). Most of the original data set for the current study had been collected on
children in public schools, at Head Start program locations, during WIC visits, at day
care centers, or during primary care physician office visits as part of the CLPPP
implementation in Marion County, Indiana. Therefore, the use of a convenience sampling
method for this study was fully justified.
Justification of Sampling Criteria
The reason for using the first sampling criterion was that children may be tested
multiple times, either using venous or capillary blood. However, many jurisdictions,
including Marion County, Indiana, require a test result to be confirmed before making the
diagnostic designation of elevated blood lead and subsequent case management (Indiana
Administrative Code, 2007; Michel et al., 2020). However, the time to confirm an EBLL
depends on the level of the initial blood tests (Mayans, 2019). Table 1 shows the CDC
recommendations for test confirmation schedule, which were also adopted during the
collection of the data set for this study.

47
Table 1
CDC Recommendation for Venous Blood Lead Level Confirmation Schedule
Blood lead level (µg/dL)
Time to confirmation testing
≥ 5
1 to 3 months
10–44
1 week to 1 month
45–59
48 hours
60–69
24 hours
≥ 70
Urgently, as an emergency test
The rationale for using the second selection criterion was that children less than 6
years old are widely reported to be the most vulnerable to lead exposure. The impact of
lead exposure on this segment of the population has been associated with a long-term
effect on children’s health, development, and academic performance (Hauptman et al.,
2017; Mayans, 2019; Sorensen et al., 2019). The analysis of a data set limited to younger
children’s blood lead content may yield useful evidence that could be integrated into
future lead exposure prevention.
The rationale for using the third sampling criterion was that there are two
outcomes for children enrolled in case management: case-completed and administratively
closed case children. Case-completed refers to a child who has at least two consecutive
blood lead test results lower than the reference value within 6 months. An
administratively closed case is one in which a child enrolled in a case of management
program has moved to another county or state (Indiana Administrative Code, 2007). The
use of the third sampling criterion restricted the data set for this study to contain only

48
case-completed children. Most public health jurisdictions follow the CDC
recommendation or establish their specific follow-up schedule for case management of
EBLL (Michel et al., 2020). Table 2 shows the follow-up schedule for EBLL in Marion
County, Indiana.
Table 2
Schedule for Follow-Up Blood Lead Testing in Marion County IN
Venous blood lead level (µg/dL)
Early follow-up for two to
four tests after identification
Later follow-up, after blood
lead levels declining
5 to 9
3 months
6 to 9 months
10 to 19
1 to 3 months
3 to 6 months
20 to 24
1 to 3 months
1 to 3 months
25 to 44
2 weeks to 1 month
1 month
≥ 45
As soon as possible
As soon as possible
Note. Adapted from MCPHD (n.d.).
Variables
The dependent variable in this study was children’s BLL in micrograms per
deciliter (µg/dL). Blood lead measurements can be obtained from capillary or venous
blood specimens (CDC, 2019a). In Marion County, Indiana, one measurement from a
venous blood specimen is sufficient to confirm an EBLL status. However, an EBLL from
capillary blood needs to be confirmed by a subsequent EBLL from a venous blood lead
test or two consecutive capillary blood lead tests carried out within a maximum of 2-
week period (Indiana Administrative Code, 2007). The independent variables include the
following:

49
• the severity of BLL at baseline,
• post-case-management time,
• parental education,
• parental race,
• parental income, and
• children’s zip code.
Severity at baseline, post-case-management time, and zip code were coded as
ordinal variables. Severity at baseline had four levels corresponding to the blood groups
described in Table 1. Post-case-management time had five levels matching the follow-up
schedule described in Table 2.
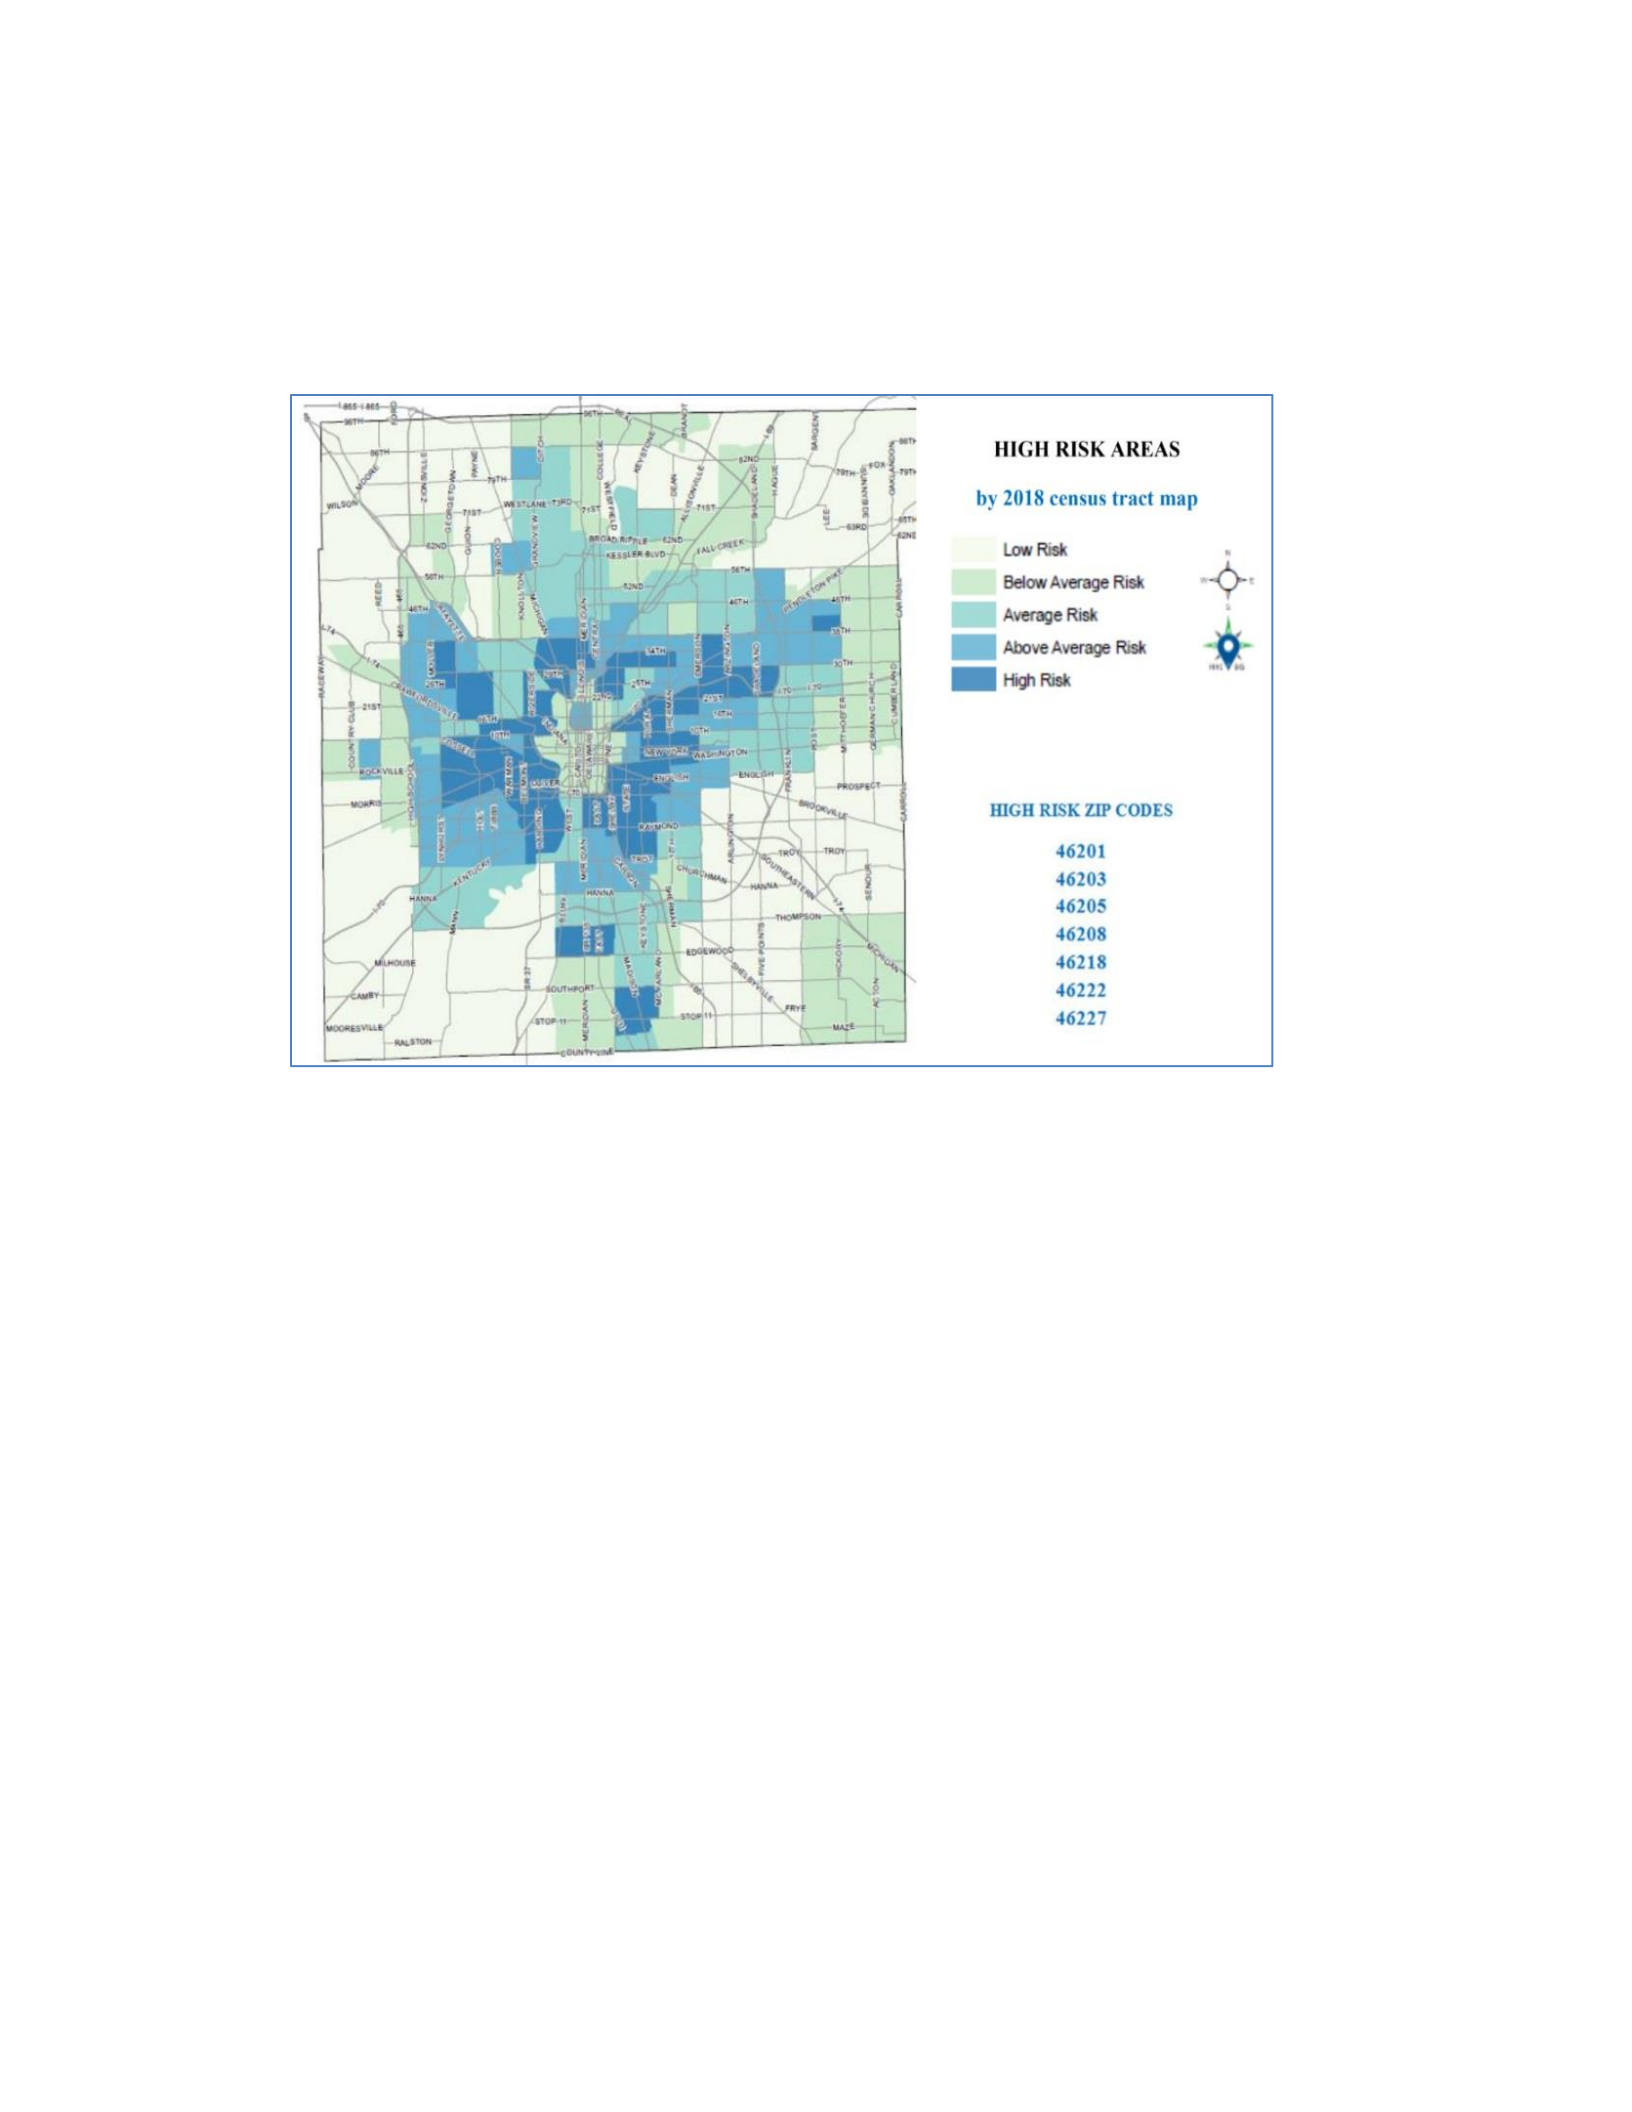
50
Figure 1
Lead Risk Level of Marion County, IN Zip Codes
Note. Adapted from MCPHD (n.d.).
MCPHD (n.d.) established lead exposure risk levels for each zip code in the
county (see Figure 1). This map was used to group children’s BLL measurements in three
categories:
• high lead risk zone,
• medium lead risk zone, and
• low lead risk zone.
Parental race and ethnicity, education, and income were nominal variables. Race
and ethnicity had four levels:
• Black,

51
• White,
• Hispanic (people of Spanish origin), and
• other (subject not represented by Black, White, or Hispanic).
Parental education was coded in four education levels:
• below high school level,
• high school graduates,
• college graduate, and
• other (parents whose education does not fit in Education Level 1, 2, or 3)
Parental income had two levels:
• Medicaid and
• non-Medicaid.
Data Analysis Plan
Data analysis will be performed with SPSS version V27 (IBM, n.d.). Before
analysis, the dataset will be cleaned to ensure that incomplete records, unknown values,
and duplicate records are removed. Also, missing data will be handled following SPSS
default settings (IBM, n.d.).
There will be two stages of statistical analysis. First, a descriptive analysis will be
performed to generate the measures of central tendency and measures of dispersion of the
dataset (Daniel & Cross, 2013; IBM, n.d). This will include the calculation of the mean,
median, mode, and standard deviation (SD) of children’s blood lead measurements.
These statistics will be stratified study subject socioeconomic factors such as race,
gender, and parental education level. The second level of analysis will involve inferential

52
statistics including simple T-TEST, ANOVA, and Multiple Linear Regression (MLR)
(Daniel & Cross, 2013; IBM, n.d). These inferential statistics techniques will help to
answer research questions 1, 2, and 3 respectively. However, before executing these
statistical techniques, a diagnostic analysis will be performed to verify that the
assumptions of each inferential statistical technique are met. If assumptions were not met,
then appropriate alternative methods will be used. For example, the Kruskal-Wallis be a
non-parametric alternative to the ANOVA if assumptions were not met. Also, the Mann-
Whitney U test will be used in case children’s blood lead measurements are not normally
distributed (Daniel & Cross, 2013; Lund Research, 2013).
Threats to Validity
Two types of validity, including internal and external validity, are frequently
addressed in most research studies (Szklo & Nieto, 2019). Internal validity refers to the
degree to which the study will achieve what it is intended to achieve. External validity
refers to the generalizability of the result to the general population from which the study
subjects were taken (Smith et al., 2011; Szklo & Nieto, 2019).
Internal validity can be threatened by many factors, including errors in
measurement and selection of the study participants (Patino, & Ferreira, 2018). In terms
of measurement errors, it is important to mention that the blood lead values in this study
were measured following both CDC, state, and local health department protocols. Also,
only CLIA-certified laboratory test results are included in the dataset (410-IAC-29).
Besides, the CLPP data has been widely used in various research reports as evidence of

53
its validity to accurately represent childhood blood lead levels (Egan et al., 2019;
Hauptman, et al., 2017).
External validity can be is affected by the characteristic of the population on
whom the findings of the research are expected to apply as well as by the nature of the
study design (Khorsan & Crawford, 2014). In terms of design, it is important to mention
that secondary data analysis is inherently prone to weaker generalizability because the
intent of the original data collection may not much the analytical approach of the second
author (Chalamandaris et al., 2016). One strategy to limit the threat of internal and
external validity is to narrow the eligibility or inclusion criteria during sampling (Khorsan
& Crawford, 2014).
Ethical Factors
Institutional Review Board (IRB) approval was obtained from Walden University
prior to the accessing and analysis of the data. The Walden University IRB approval
number for this study is 04-12-21-0761141. This study is about children, a generally
considered vulnerable population because they do not have the intellectual and emotional
capacities to give valid informed consent (Bagattini, 2019). Moreover, the original
dataset that contains children blood lead measurements also contains the following
information: children’s full name, date of birth (DOB), gender, full address, county of
residence, race and ethnicity, parent or guardian’s name and phone number, and
information required to receive federal funding (ISDH, 2017; 2018). These are
individually identifiable information that misuse could lead to HIPPA violations (HIPPA

54
Journal, 2018). These considerations imply extra vigilance and caution to protect children
and parents’ privacy and avoid causing children some harm (Bagattini, 2019).
This study will take the following steps to minimize the risk of ethical issues. One
step is to obtain Institutional Review Board (IRB) approval from both Walden University
as well as from the Marion County Public Health Department. The second step is to apply
the principle of both Safe Harbor and Expert Determination (HIPPA Journal, 2017).
Applying the Safe Harbor will consist of de-identifying children in the study dataset by
removing selected information such as full name, DOB, full address, parent, and
guardians’ contact information. Applying the Expert Determination strategy will consist
of obtaining an opinion from a statistical expert at Walden University.
Age, gender, and zip code will however be used with caution because they are
relevant to answer the research questions. But zip codes with less than 5 elevated blood
level records will be excluded to avoid violation of the principle of Protected Health
Information [PHI] (HIPPA Journal, 2018).
Summary
This study is designed as a quantitative retrospective cohort research with a
convenient sampling technique. It is essentially a secondary analysis of data from the
CLPP conducted in Marion County, IN. from January 1, 2018, to December 31st, 2019.
CLPP is a nationally recognized program and its data have been wildly used to describe
the prevalence of lead exposure across the US (Egan et al., 2019; Hauptman, et al., 2017).
I believe that the popularity of this CLPP program contributes to the validity of the data
set in this study.

55
In the methodology section, I detailed many important research elements
including the study population, the sampling strategy, the variables, and the data analysis
plan. In terms of the study population, this research works is about children who had
confirmed EBLL in Marion County, IN., during the 2018 and 2019 CLPP and when
using a reference blood lead level of ≥5µg/dL (ISDH, 2017; 2018).
The dependent variable is children’s blood lead content in micrograms per
deciliter (µg/dL). The independent variables include 1) severity of blood lead level at
baseline, 2) post-case management time, 3) parental education 4) race and ethnicity, 5)
parental income, and 6) zip code. The following inferential statistics will be used for
answering the research questions: simple T-TEST, ANOVA, and Multiple Linear
Regression (MLR). For each of these parametric methods, I plan an alternative non-
parametric approach if the data fail to conform to the assumption of the parametric
method (Daniel & Cross, 2013; Lund Research, 2013).
In this study, ethical questions are related to parental consent and confidentiality
of children’s identity (Bagattini, 2019). To respect these ethical considerations this study
will seek Institutional Review Board (IRB) approval from both Walden University as
well as from the Marion County Public Health Department. Also, data that can
potentially be used to identify a study subject will be removed. For example, zip codes
with less than 5 records will be excluded (HIPPA Journal, 2017; 2018). I believed that
this detailed description of the methodology will allow this study to be replicated if
needed.

56
Chapter 4: Results
Childhood lead poisoning continues to be a public health problem in many
communities in the United States (Mayans, 2019). In Marion County, Indiana, children
diagnosed with EBLL (≥ 5 µg/dL) are provided case management and follow-up services
including (a) home inspections by a state-certified lead inspector; (b) education for
parents and guardians about lead hazards and the importance of good nutrition for the
prevention and treatment of lead exposure; and (c) referring children to social programs
that provide additional help for improving child health, nutrition, and education (Delgado
et al., 2018; Michel et al., 2020). However, researchers had not evaluated the
effectiveness of these services in bringing children’s BLL below the reference level of 5
µg/dL in Marion County, Indiana. The purpose of the current study was to fill that gap. I
sought to answer three questions: (a) Is there a difference between blood lead level at
baseline and blood lead level at post-case-management time? (b) Is there a difference
between blood lead level at baseline and blood lead level at post-case-management time
that may be modifiable by race, zip code of residence, or poverty level? and (c) Can the
difference between baseline and post-case-management be modified by the severity of
blood lead content at baseline?
To answer these questions, I analyzed childhood lead case management records
from Marion County, Indiana, for the period between January 1, 2018, and December 31,
2019. In this chapter, I explain the data extraction process and the sample subjects’
inclusion–exclusion criteria. I also describe the independent and dependent variables. In
addition, I present the results of the test the normality assumption of the variables and

57
provide descriptive statistics of the variables. I used appropriate inferential statistical
methods to answer each research question. Finally, I use tables and graphs to summarize
the results of these statistical methods.
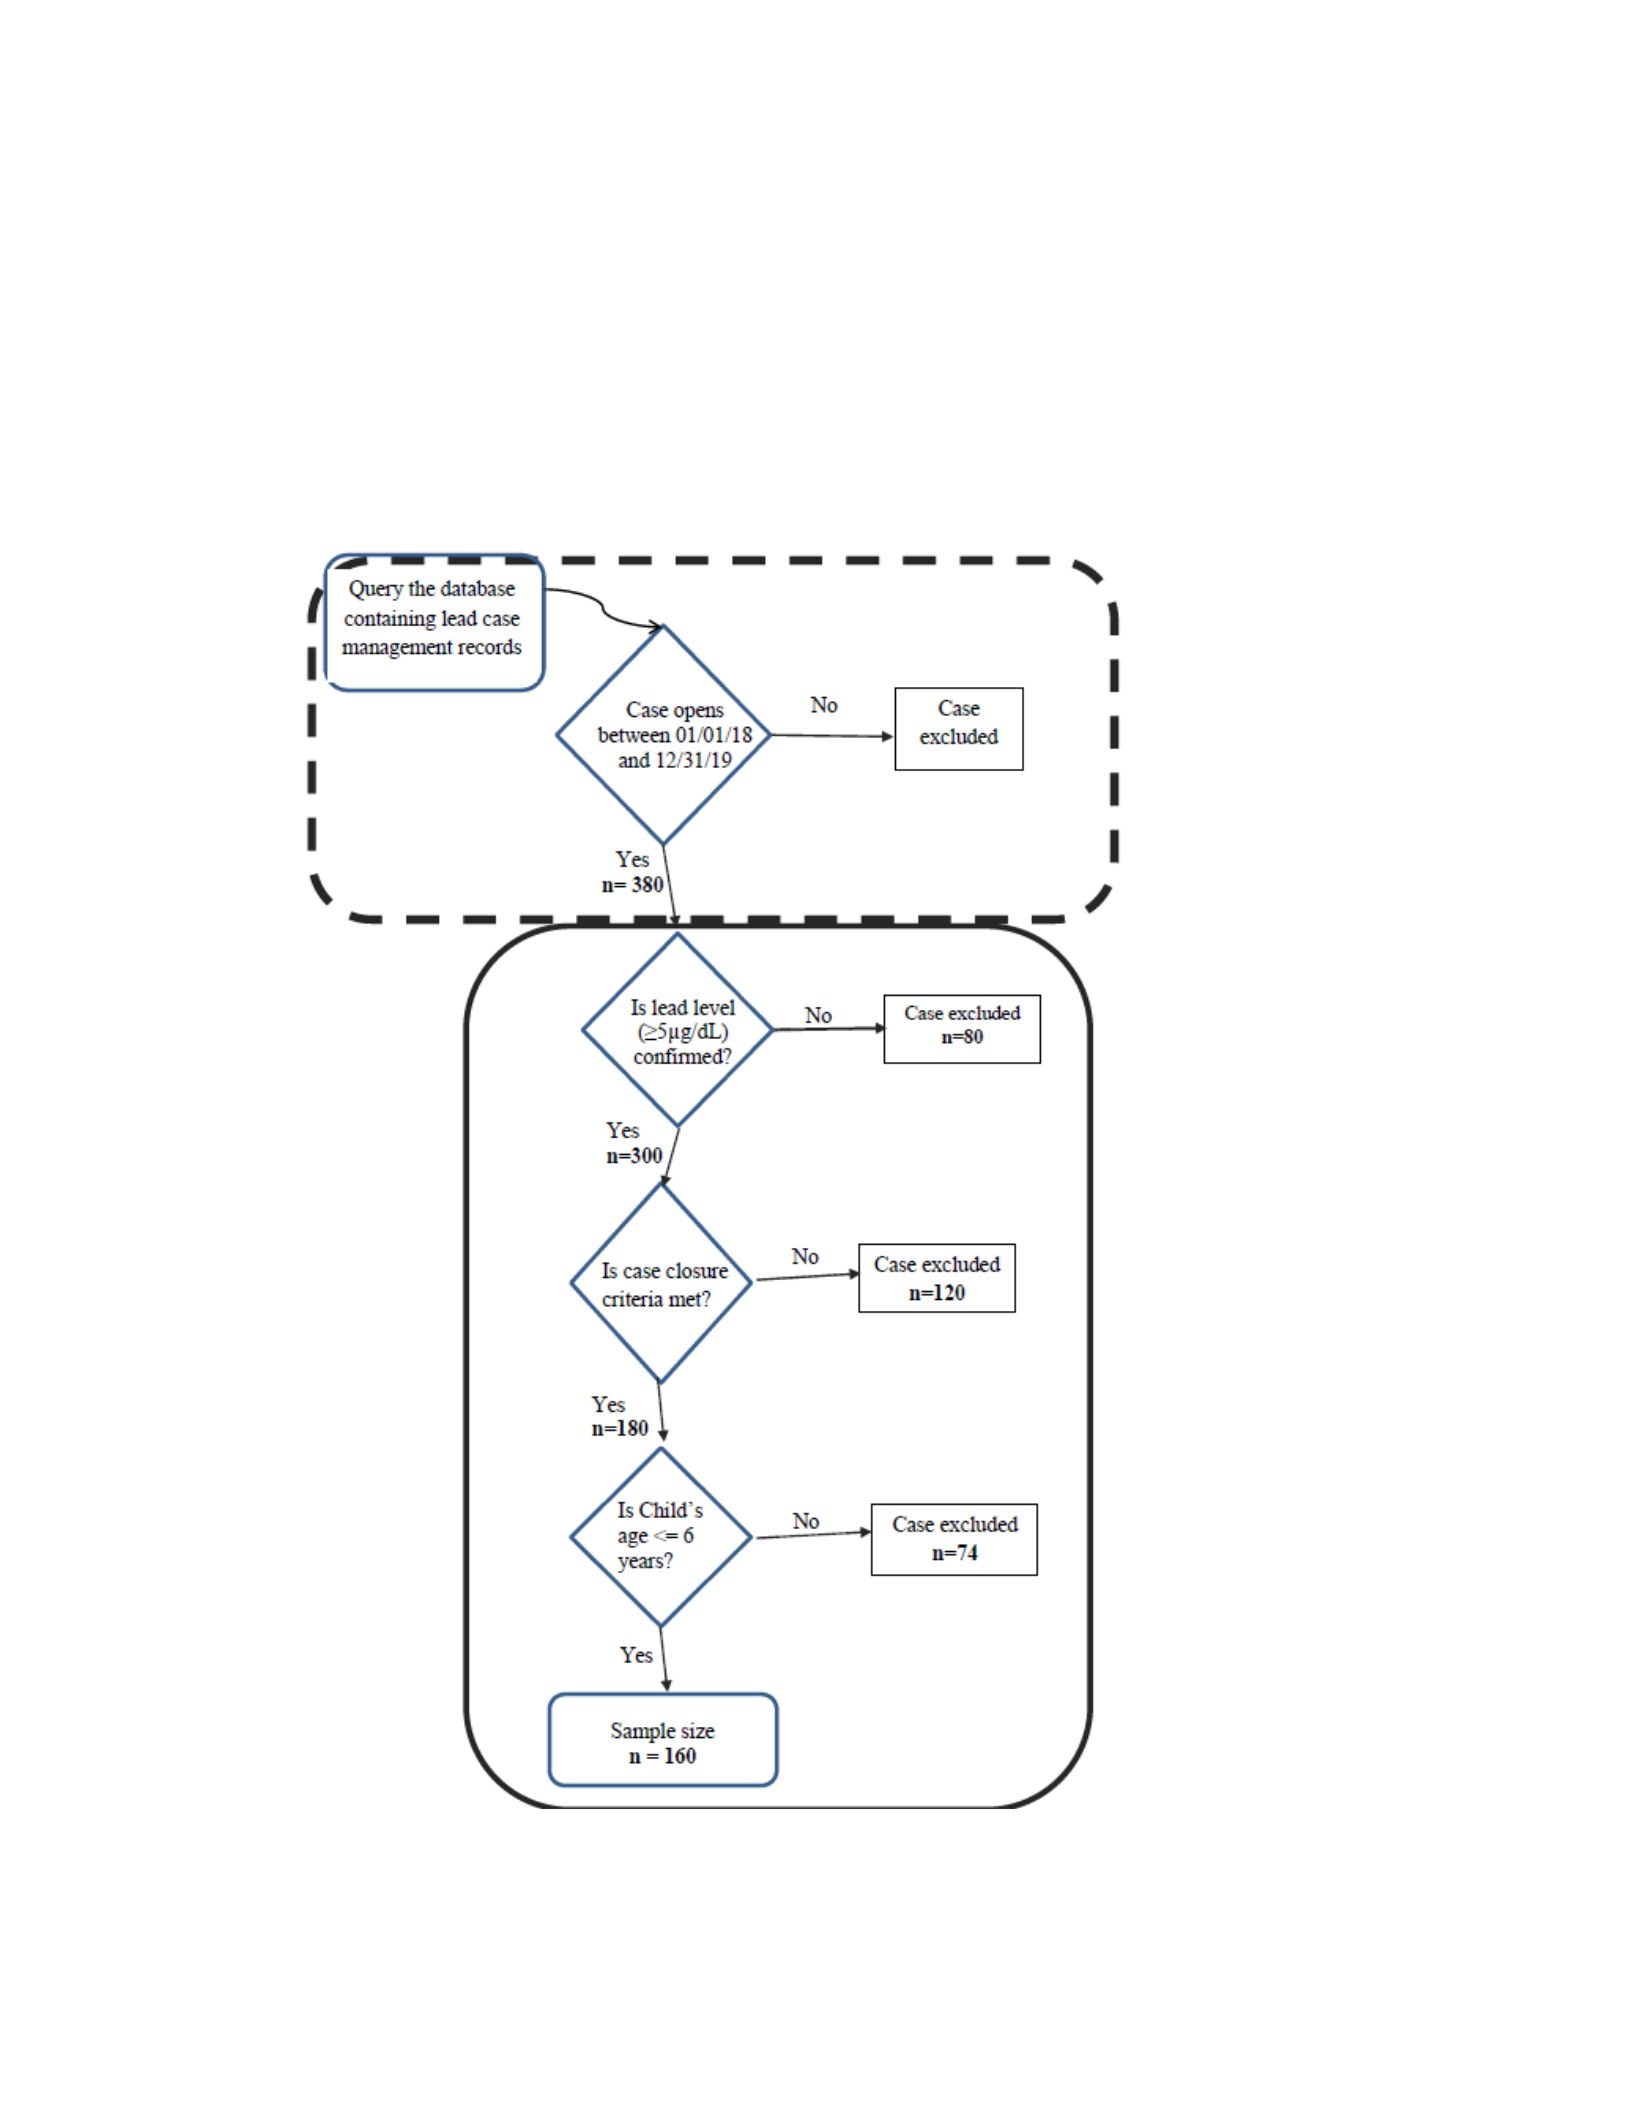
58
Data Collection
Data Extraction
Figure 2
Flowchart of the Inclusion–Exclusion Process

59
The data used in this research were accessed in two steps as shown in Figure 1.
First (broken line) the database that hosts blood lead exposure case management records
was queried to obtain cases that were opened and closed between January 1, 2018, and
December 31, 19. Second (solid line), each case was subsequently queried, and the
inclusion–exclusion criteria were applied.
Inclusion–Exclusion Criteria
A case was excluded from the study if any of the following were not satisfied: (a)
the age of the subject was less than or equal to 6 years, (b) the case was confirmed by a
venous blood test or by two successive capillary blood tests, and (c) the case was closed
with the comment “met closure criteria.” A total of 380 cases were opened between
January 1, 2018, and December 31, 2019. At the end of this two-step process, the final
sample size for this study was 160 cases.
Variables
The dependent variable in this study was the children’s blood lead content (blc) in
microgram per deciliter (µg/dL). Blc was measured as a continuous variable with one
decimal level. The independent variables included (a) post-case-management time
(checkup), (b) severity of lead exposure at baseline (severity), (c) the lead risk status in
zip code of residence (risk), and the poverty status (Medicaid) of the child at the time of
registration for case management. The variable checkup was recorded on an ordinal scale.
It represented the number of times a subject had a blood test during their case
management follow-up. Therefore, the level of variable checkup varied by subject. Most

60
subjects (94.4%) had three checkups while a small number (5.6%) had four checkups
during the case management.
The severity variable was also recorded as an ordinal variable with two levels
including Severity Level 1 (blood lead content ≤ 9 µg/dL) and Severity Level 2 (blood
lead content between 10 and 44 µg/dL). Variable risk was on an ordinal scale with three
levels: (a) high lead risk zip code (High risk), medium lead risk zone (Medium risk), and
low lead risk zones (Low risk). Variable poverty was measured on a nominal scale with
two levels: (a) Yes = Medicaid and (b) No = non-Medicaid. Race, age, and gender of the
subjects were recorded as covariates. In this study, race had four groups: Asian, Black,
Latino, and White. Age had three groups: <1 year, 1–3 years, and 4–6 years. Gender had
two groups: male and female.

61
Table 3
Descriptive Statistics of Blood Lead Level at Baseline
Arithmetic statistics
Geometric statistics
Covariates
N (%)
Mean
SD
Median
Mean
SD
Median
Age (year)
< 1
8 (5%)
8.6
3.8
8.0
8.0
1.4
8.0
1–3
128 (80%)
8.3
3.4
7.0
7.7
1.4
7.0
4–6
24 (15%)
8.1
3.1
7.5
7.6
1.6
7.4
Gender
Female
72 (45%)
8.3
3.5
7.0
7.7
1.4
7.0
Male
88 (55%)
8.3
3.2
8.0
7.7
1.4
8.0
Race
Asian
30 (19%)
7.2
2.6
6.0
6.8
1.3
6.0
Black
44 (27%)
7.8
2.6
7.0
7.3
1.3
7.0
Latino
49 (31%)
9.2
3.5
8.0
8.5
1.4
8.0
White
37 (23%)
8.7
4.2
7.0
7.9
1.5
7.0
Zip code
High risk
101 (63%)
8.6
3.4
8.0
8.0
1.4
8.0
Medium risk
21 (13%)
8.2
3.9
7.0
7.6
1.4
7.0
Low risk
38 (24%)
7.5
2.9
6.5
7.1
1.4
6.4
Medicaid
Yes
98 (61%)
8.6
3.3
8.0
8.0
1.4
8.0
No
62 (39%)
7.7
3.3
6.6
7.2
1.4
6.4
Severity
≤ 9 µg/dL
121 (76%)
6.7
1.6
6.0
6.6
1.2
6.0
10 to 44 µg/dL
39 (24%)
13.1
2.8
12.0
12.8
1.2
12.0

62
Frequency Distribution
Table 3 shows descriptive statistics of the dependent variable blc stratified by
covariates. Considering age, children between the ages of 1 year and 3 years constituted
80% of the cases. Children between the ages of 4 years and 6 years represented 15% of
the sample while children less than 1 year old represented 4% of the sample.
Considering gender, most cases (55%) were male compared to 45% female. In
terms of race, Latinos accounted for most of the cases (31%), followed by Blacks (27%),
Whites (23%), and Asians (19%). Considering zip code of residence, most cases (63%)
came from zip codes with high lead risk. Low lead risk zip codes and medium lead risk
zip codes accounted for 24% and 13% of the cases, respectively.
Table 3 also indicates that 76% of cases were Severity Level 1 (baseline blood
lead content ≤ 9µg/dL) while the remaining 24% of cases were Severity Level 2 (baseline
blood lead content between 10 and 44 µg/dL). In addition, stratification by poverty level
indicated that up to 61% of children qualified for Medicaid at the time of registration of
case management.
Blood Lead Content
Table 3 shows that children below the age of 1 year had the highest geometric
mean BLL (8.0 µg/dL) compared with the other age groups. Males and females showed
no difference in terms of mean BLL. Each group had a geometric mean BLL of 7.0
µg/dL. The difference in blood lead content between racial groups was more pronounced.
The Latino group had the highest geometric mean BLL (8.5 µg/dL) followed by Whites
(7.9 µg/dL), Blacks (7.3 µg/dL), and Asians (6.8 µg/dL), respectively. Zip code variable

63
also showed clear differences in terms of mean BLL. Children living in zip codes with
high lead risk had geometric mean blood lead content of 8.0 µg/dL compared with 7.6
µg/dLfor medium lead risk zip codes and low lead risk zip codes (7.1 µg/dL). In respect
to the poverty variable, Table 4 shows that Medicaid-eligible children had a higher
geometric mean of blood lead content (8.0 µg/dL) compared with children who were not
Medicaid eligible (7.2 µg/dL).
Table 4
Descriptive Statistics of Blood Lead Level at Baseline and Post-Case-Management
Checkup
Arithmetic statistics
Geometric statistics
Baseline and post-case-
management time
N
Mean
(µg/dL)
SD
Median
(µg/dL)
Mean
(µg/dL)
SD
Median
µg/dL
Baseline
160
8.3
3.4
7.5
7.7
1.4
7.0
First checkup
160
7.2
2.8
4.0
4.4
1.7
4.0
Second checkup
76
6.5
2.0
4.0
4.4
1.4
4.0
Third checkup
32
5.5
1.3
4.0
3.8
1.4
4.0
Fourth checkup
10
3.3
1.1
3.0
3.0
1.6
4.0
Table 4 shows descriptive statistics of the dependent variable blc at baseline and
at post-case-management time (checkups). As expected, the mean BLL at baseline
(before case management started) was the highest (geometric mean =7.7µg/dL) while the
mean blood lead content at the fourth checkup (geometric mean = 3.0 µg/dL) was the
lowest.

64
Table 5
Prevalence of EBLL at Baseline and at Post-Case-Management Checkup
EBLL+
EBLL-
Post case
management time
N
%
N
%
Baseline
160
100
0
0
1st checkup
76
47.5
84
52.5
2nd checkup
32
43.7
44
56.3
3rd checkup
10
30.3
22
69.7
4th checkup
0
0.0
10
100
Table 5 shows that 52.5% of children diagnosed with [EBLL] recovered by their
1st checkup time after going through case management intervention (EBLL =52.5%). By
the 3rd checkup, 94 % [(160-10)/160) *100)] of the children got their blood lead level
below the reference level of 5.0 µg/dL. Only a relatively small percentage (about 6%) of
children had to get to their 4th checkup before their blood lead level drop below the
reference value of 5.0 µg/dL. These trends are graphically represented in Figure 3 where
Nb represents the number of children at each checkup and % represents the percentage.
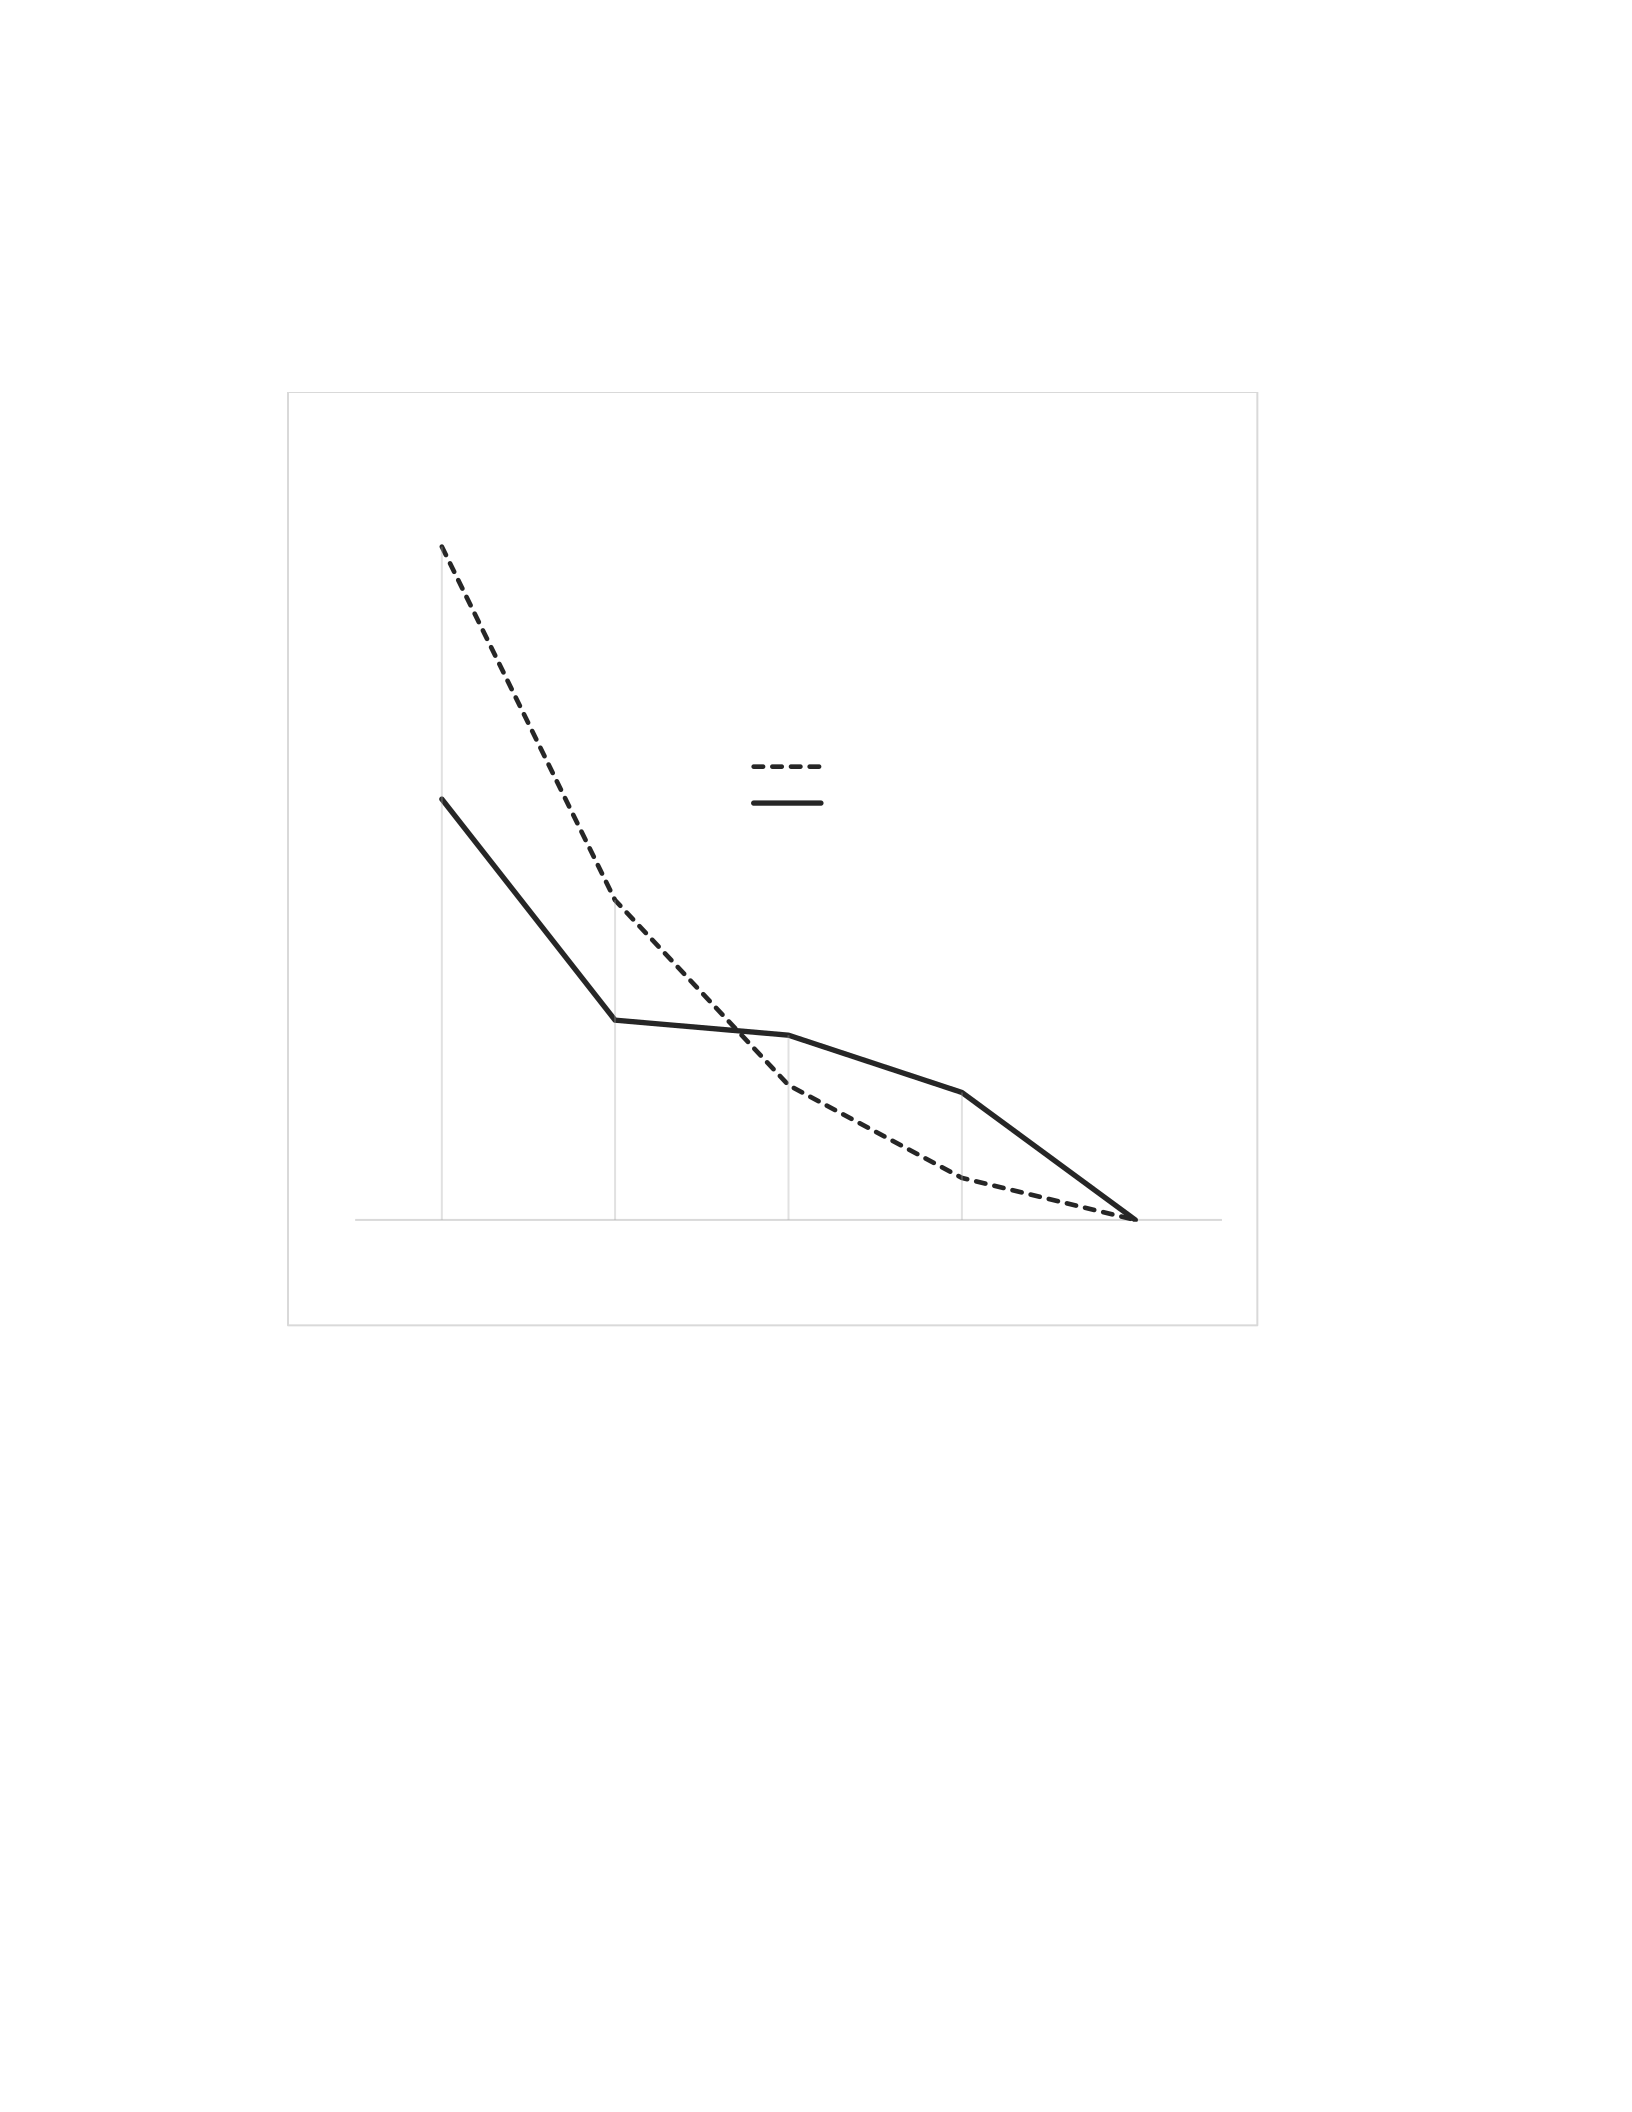
65
Figure 3
Trend of the Prevalence of EBLL at Baseline and Post-Case-Management Checkup
Inferential Statistics
Normality Assumption
Checking for normality assumption is a critical step in the choice of appropriate
statistical methods for research data. For example, if a variable is normally distributed
then many parametric methods such as ANOVA, t-test, or regression analysis can be
applied to the variable. However, if the normality assumption is violated, non-parametric
160
76
32
10 0
100
47.5 43.9
30.3
0
0
20
40
60
80
100
120
140
160
180
Baseline 1st Checkup 2nd checkup 3rd checkup 4th checkup
Nb
%
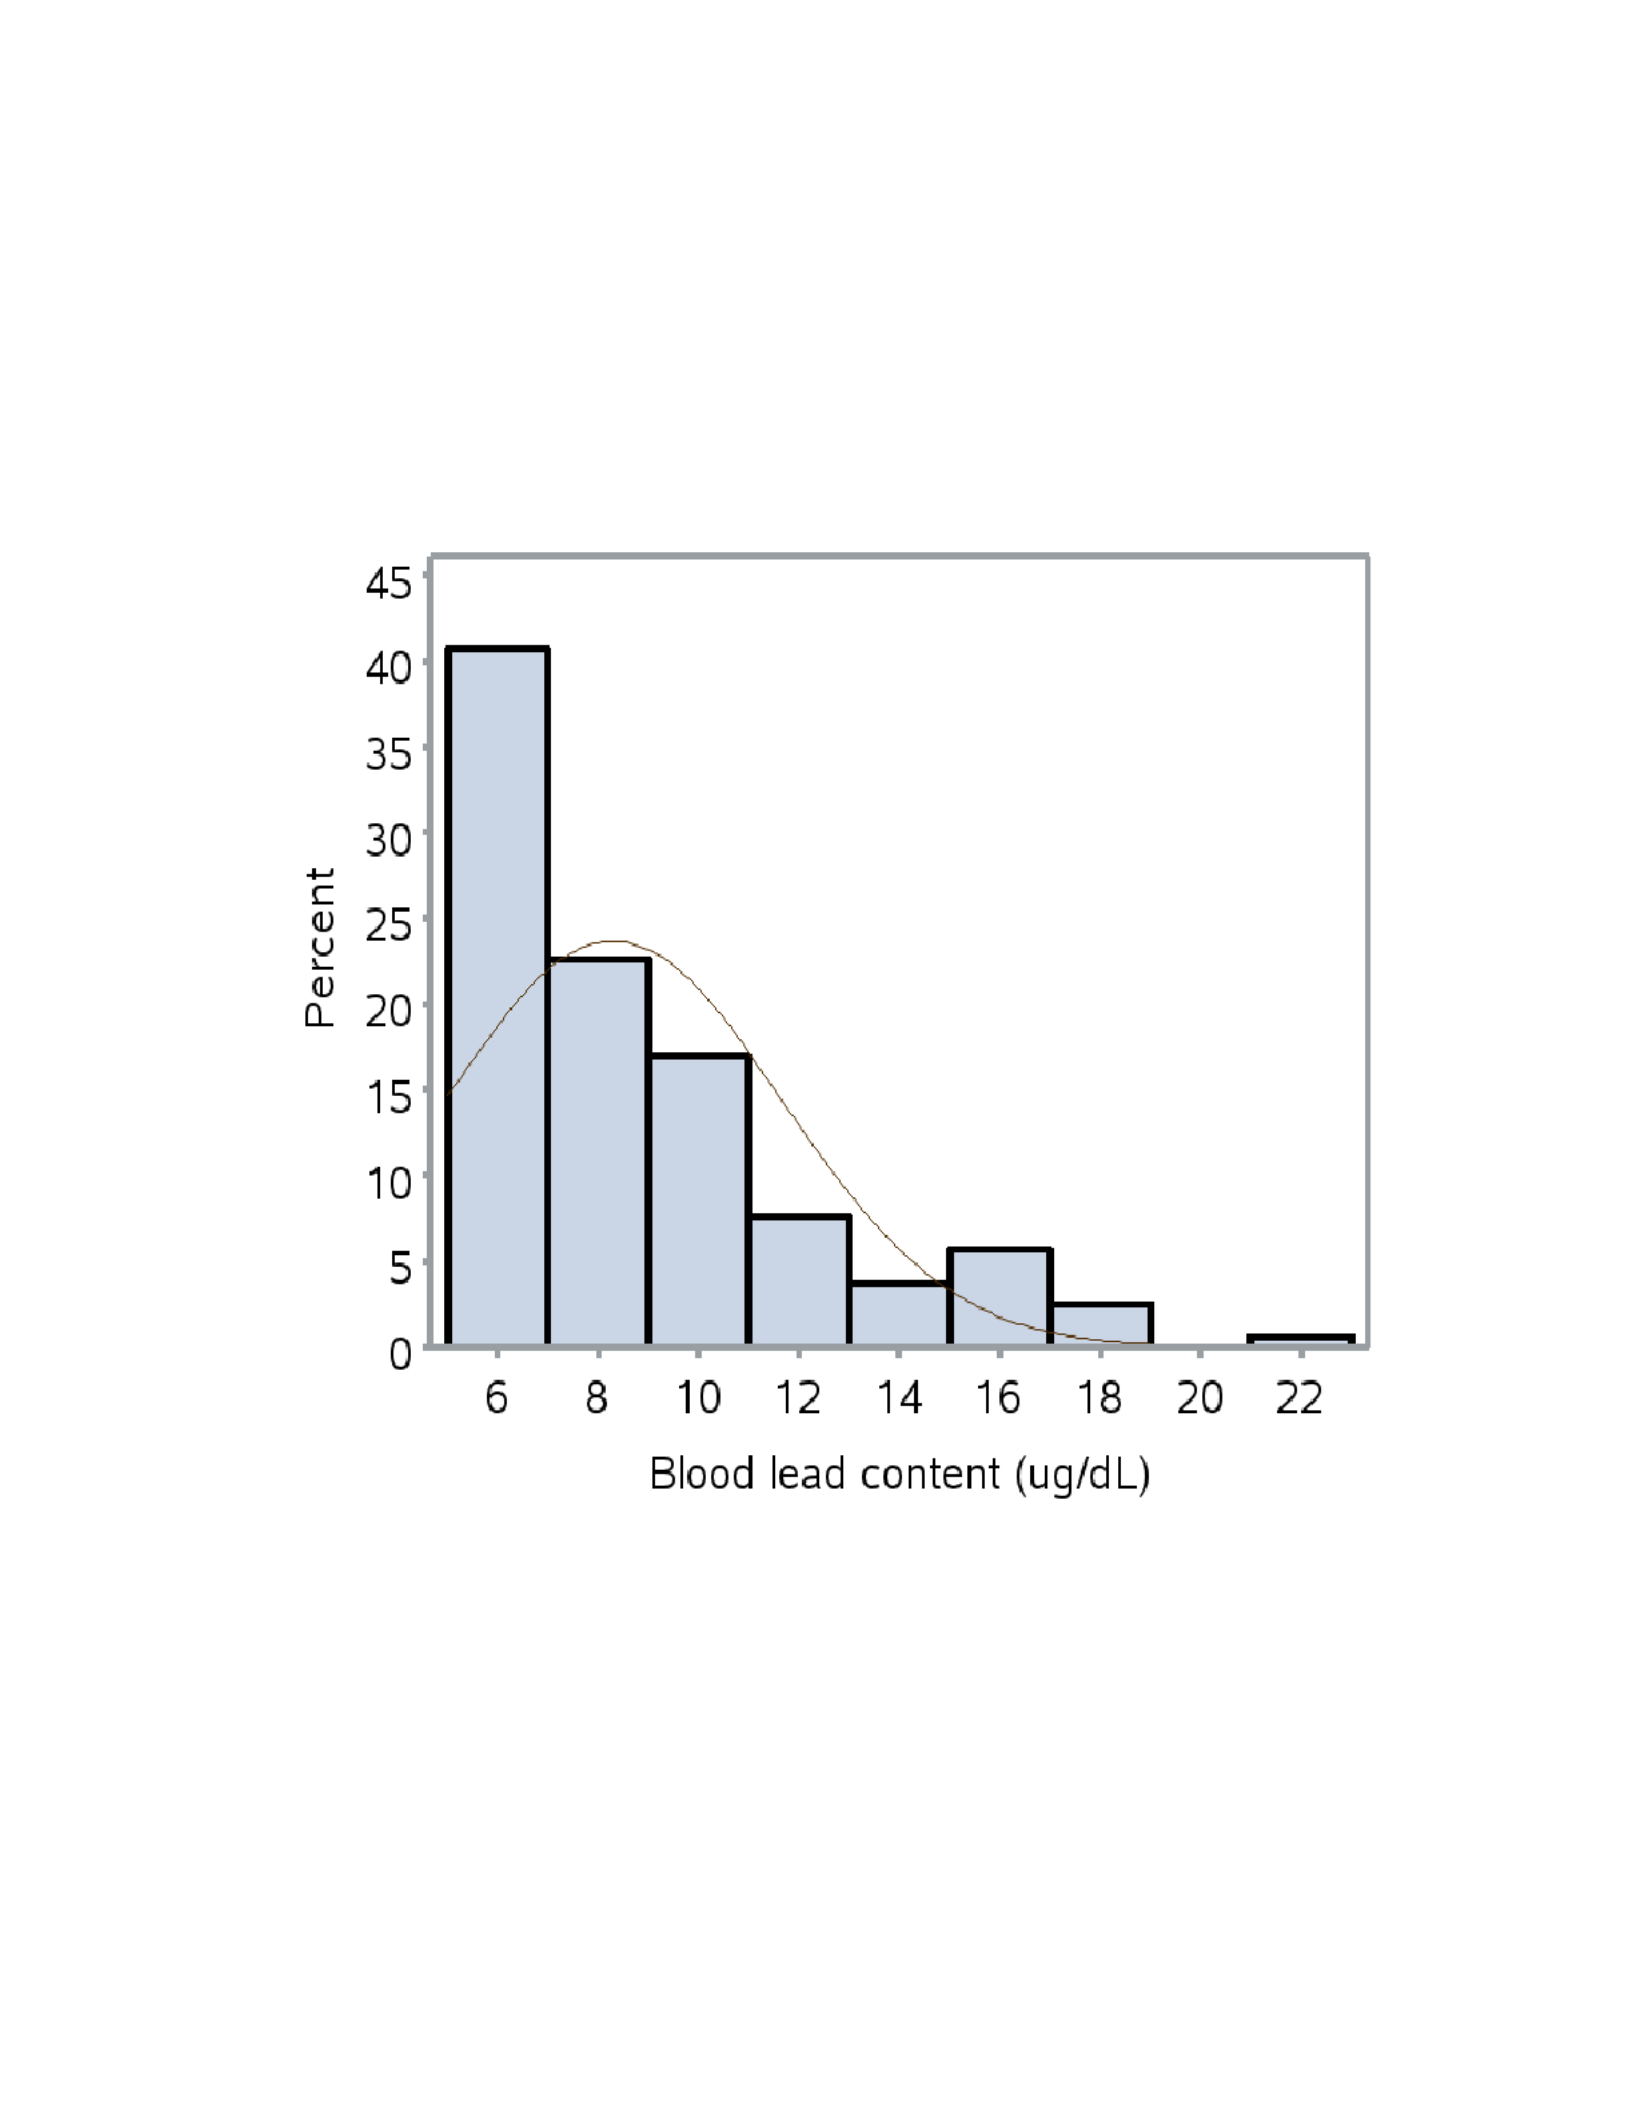
66
methods might be a more appropriate analytical approach (Daniel & Cross, 2013;
Frankfort-Nachmias & Nachmias, 2008).
Figure 4
Histogram and Normal Distribution Curve of Blood Lead Content
Checking for normality of variable can be achieved through a combination of
graphical and numerical methods including histogram, normal curve, and Kolmogorov-
Smirnov (D) or Cramer-von Mises (W-Sq) test statistics. It is generally accepted that a

67
normally distributed variable should have a bell shape curve with skewness and near-zero
(Daniel & Cross, 2013; Frankfort-Nachmias & Nachmias, 2008).
Figure 4 shows that the dependent variable for this study (blc) is not normally
distributed. The normal curve over the histogram is highly skewed to the right
(Skewedness =1.37) with a relatively large kurtosis (1.67). In addition, the goodness-of-
fit tests (D and W-Sq) for normality distribution show p-values that are less than 0.05,
which indicates a lack of normality (Daniel & Cross, 2013; Frankfort-Nachmias &
Nachmias, 2008).
Alternative Analytical Approach
Log transformation is a common approach to bringing research data to
approximate normal distribution, particularly when the data is skewed to the right (Feng
et al., 2014). However, even log transformation cannot bring the current research dataset
to an approximately normal distribution as shown in Figure 5. The Normal Quintile Plot
for both the original blc values (Figure 5a) and the log-transformed blc values (Figure 5b)
remained skewed. Consequently, I will be using nonparametric methods to answer the
research questions as suggested in Chapter 3.
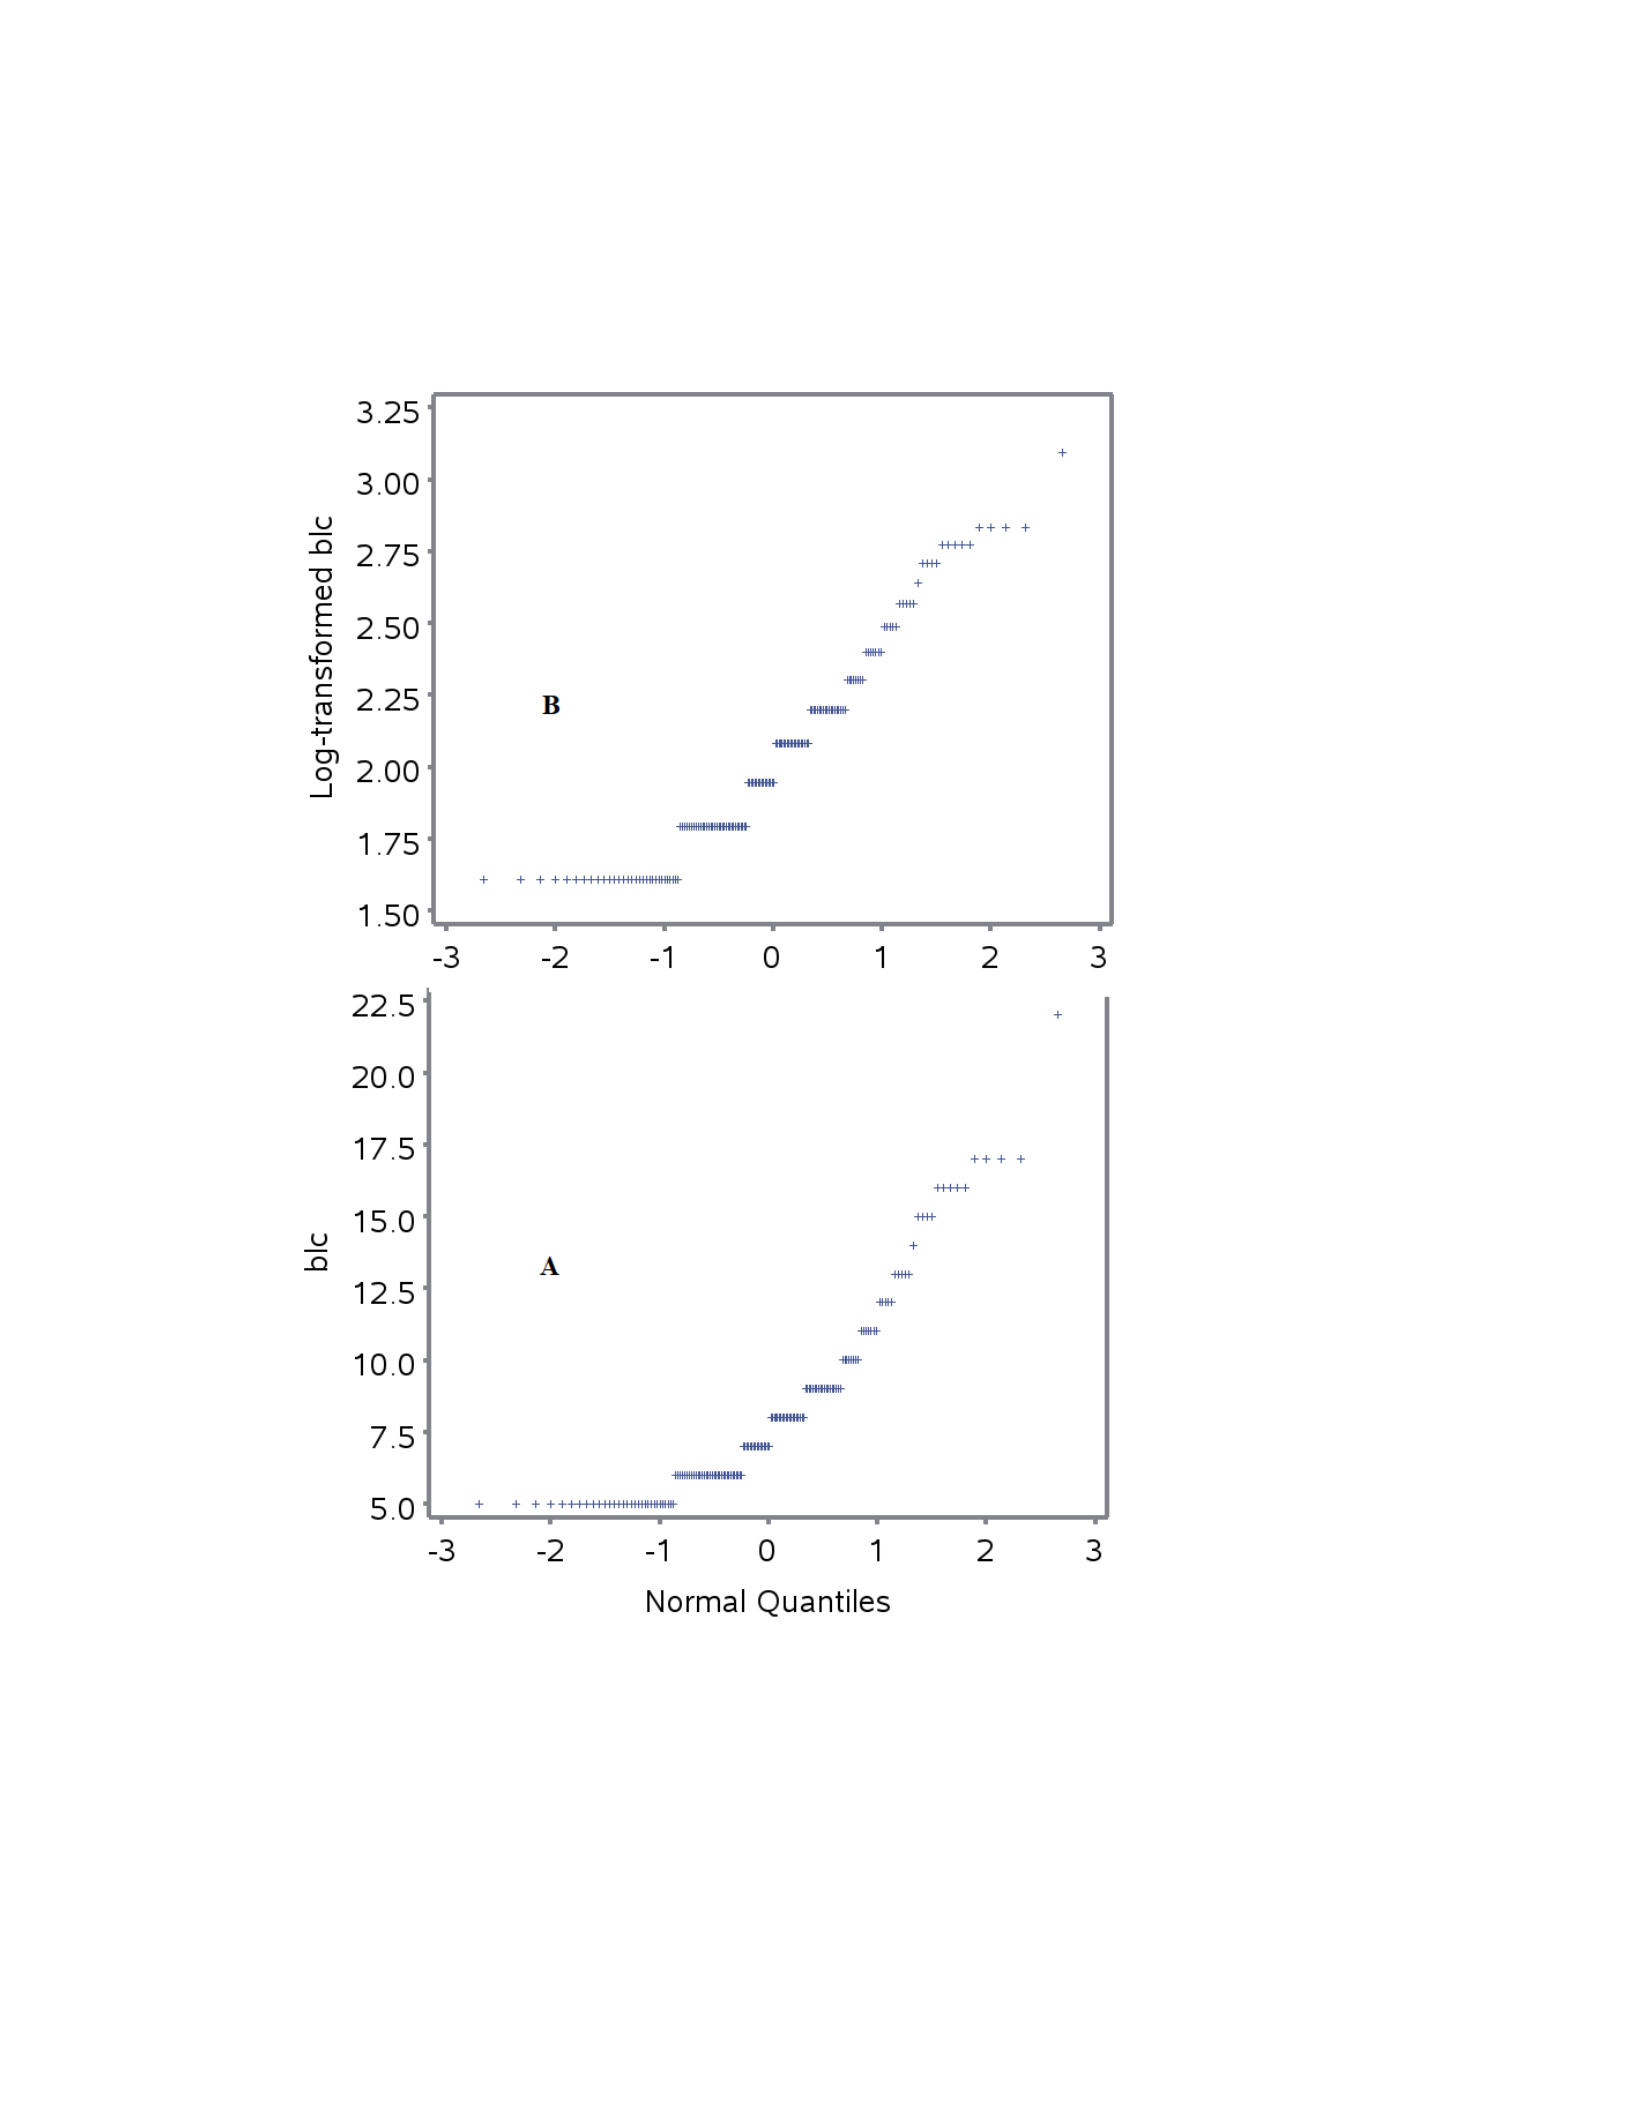
68
Figure 5
Normal Quantiles Plots for Variable blc (A) and Log-Transformed blc (B)

69
Research Question 1
The first research question in this study is: Is there a difference between blood
level at baseline and blood lead level at post-case management time? The null hypothesis
(Ho) and alternative hypothesis (Ha) at alpha = 0.05 probability level for this question
follow.
• Ho1: there is not a statistically significant difference between blood lead level
at baseline and blood lead level at post-case management time
• Ha1: there is a statistically significant difference between blood lead level at
baseline and blood lead level at post-case management time
To test these hypotheses, I used the Wilcoxon and Kruskal-Wallis statistical
methods (Daniel & Cross, 2013; Frankfort-Nachmias & Nachmias, 2008) to analyze the
data, using blc as the dependent variable and checkups as the explanatory variable. The
result of this analysis is shown in Table 6. and Figure 6.

70
Table 6
Analysis of Variance of Blood Lead Content at Baseline and Post-Case-Management
Checkup
LabTest
Sum of
Scores
Expected
under Ho
SD under
Ho
Mean
Score*
Baseline
49784.50
34880.0
1255.63
311.15a
1st checkup
27725.00
34880.0
1255.63
173.28b
2nd checkup
12237.50
15914.0
973.09
167.67b
3rd checkup
4291.50
7194.0
689.45
130.04bc
4th checkup
791.50
1962.0
370.65
87.94c
Kruskal-Wallis Test: X2 =147.67 df=4 p<0.0001
*Scores followed by the same letter are not statistically different
Table 6 shows a statistically significant difference between scores of blood lead
content at baseline and score of blood lead content at each check-up after case
management was initiated as evidenced by significant Kruskal-Wallis test statistics
(X2=147.62, df = 4, p <0.0001). Thus, the null hypothesis (Ho) must be rejected, and the
alternative hypothesis (Ha) must be accepted. In order words, there is enough statistical
evidence to declare that case management activities have a significant effect on children
blood lead level after they were diagnosed with EBLL.
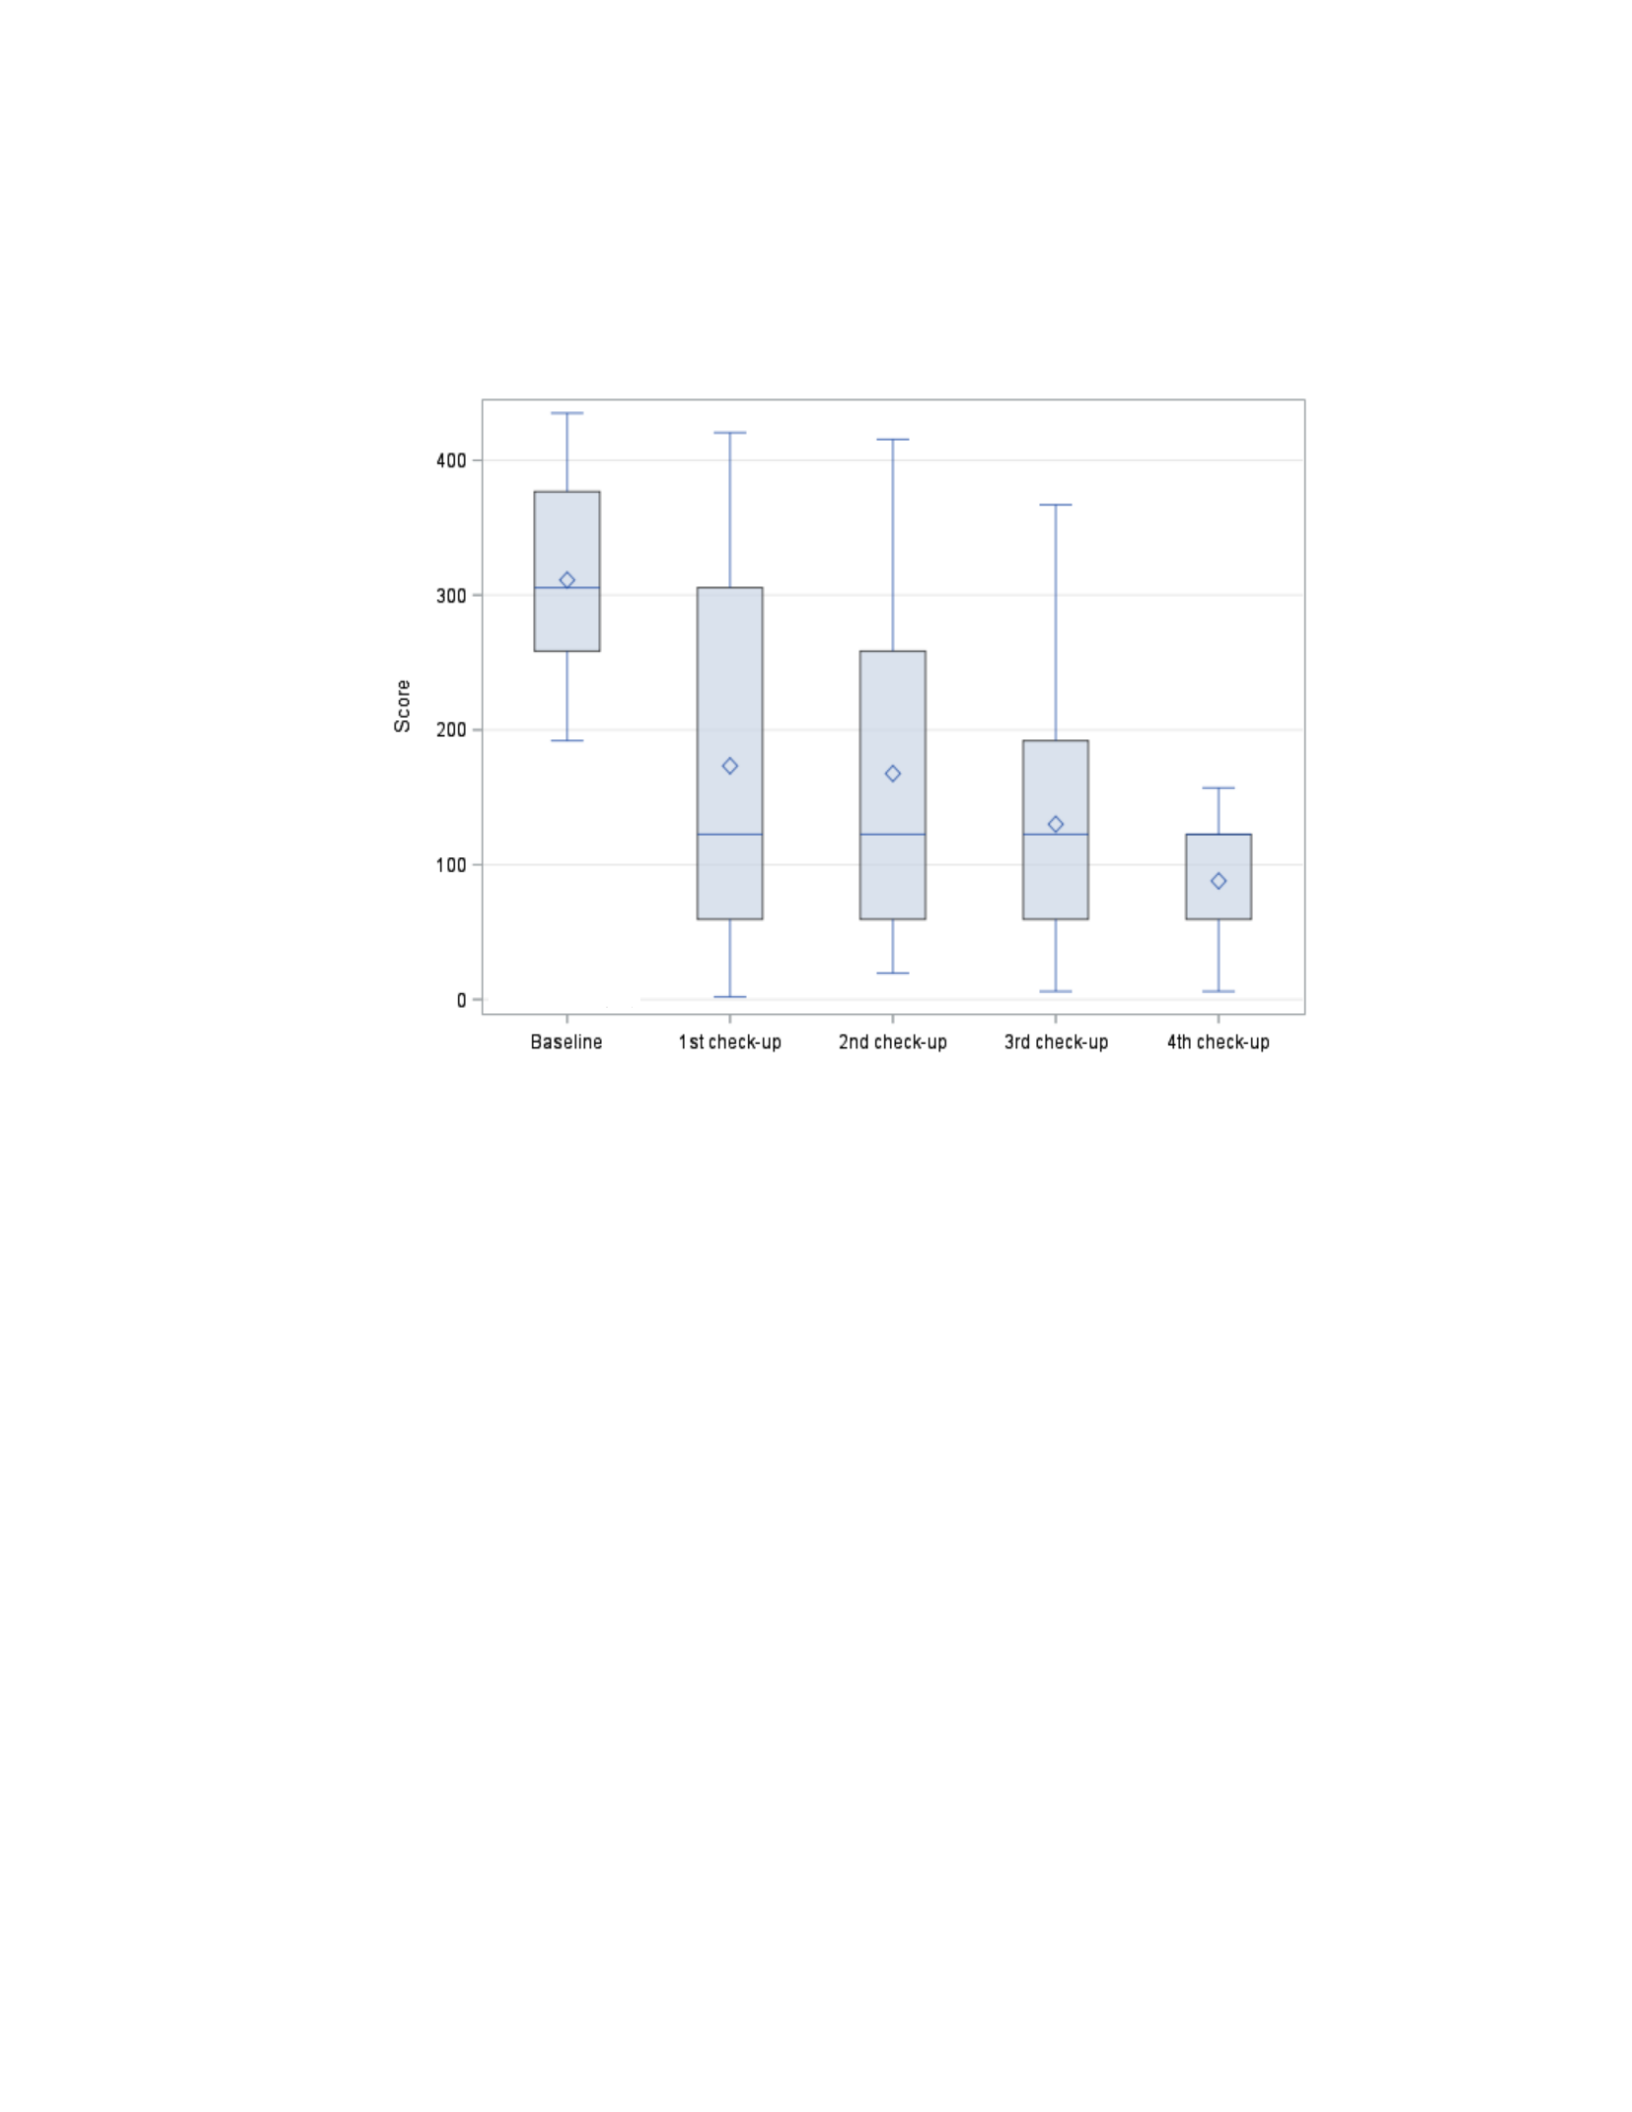
71
Figure 6
Box Plot of Mean Scores of blc at Baseline and Post-Case-Management Checkup
The mean separation column in Table 4 and the graphical representation of the
mean scores in Figure 6 suggest that there is a significant reduction in blood lead content
between the baseline and the first post case management time (1st checkup time).
However, the difference in blood lead content between 1st, 2nd, and 3rd checkups is not
statistically significant. Also, blood lead content at the 4th checkup was not statistically
significant from blood lead level at the 3rd checkup.
Research Question 2
The second question for this research study is: Is the change in blc between
checkups associated with race, zip code lead risk status, or poverty? The null hypothesis
(Ho) and alternative hypothesis (Ha) for this question considering alpha = 0.05
probability level follow

72
• Ho2: the change of blc between checkups levels is not associated with subject
race, zip code lead risk status, or poverty
• Ha2: the change between blc between checkups levels is associated with
subject race, zip code lead risk status, or poverty
To answer this question, I analyzed the data using blc as a dependent variable and
checkups as an explanatory variable while controlling independently for race, zip code,
and poverty. As in research question one, I used the Wilcoxon rank transformed scores
instead of the original blood content values because the original values were not
normality distributed (Daniel & Cross, 2013; Feng et al. 2014; Frankfort-Nachmias &
Nachmias, 2008).
Race and Case Management
Table 7
Analysis of Variance for Race and Post-Case-Management Checkup Interaction
Source
DF
Type III SS
Mean Squares
F value
Pr > F
race
3
73.468
24.489
3.21
0.0231
checkups
4
1266.734
316.683
41.48
.0001
race*checkup
10
18.364
1.836
0.24
0.990
Table 7, Figure 7, and Table 8 are about the part of research question two which is
related to the effect of race on the outcome of case management. Table 7 shows that there
is a statistically significant difference between race levels, but there is no statistically
significant interaction between race groups and checkup levels (Figure 7).
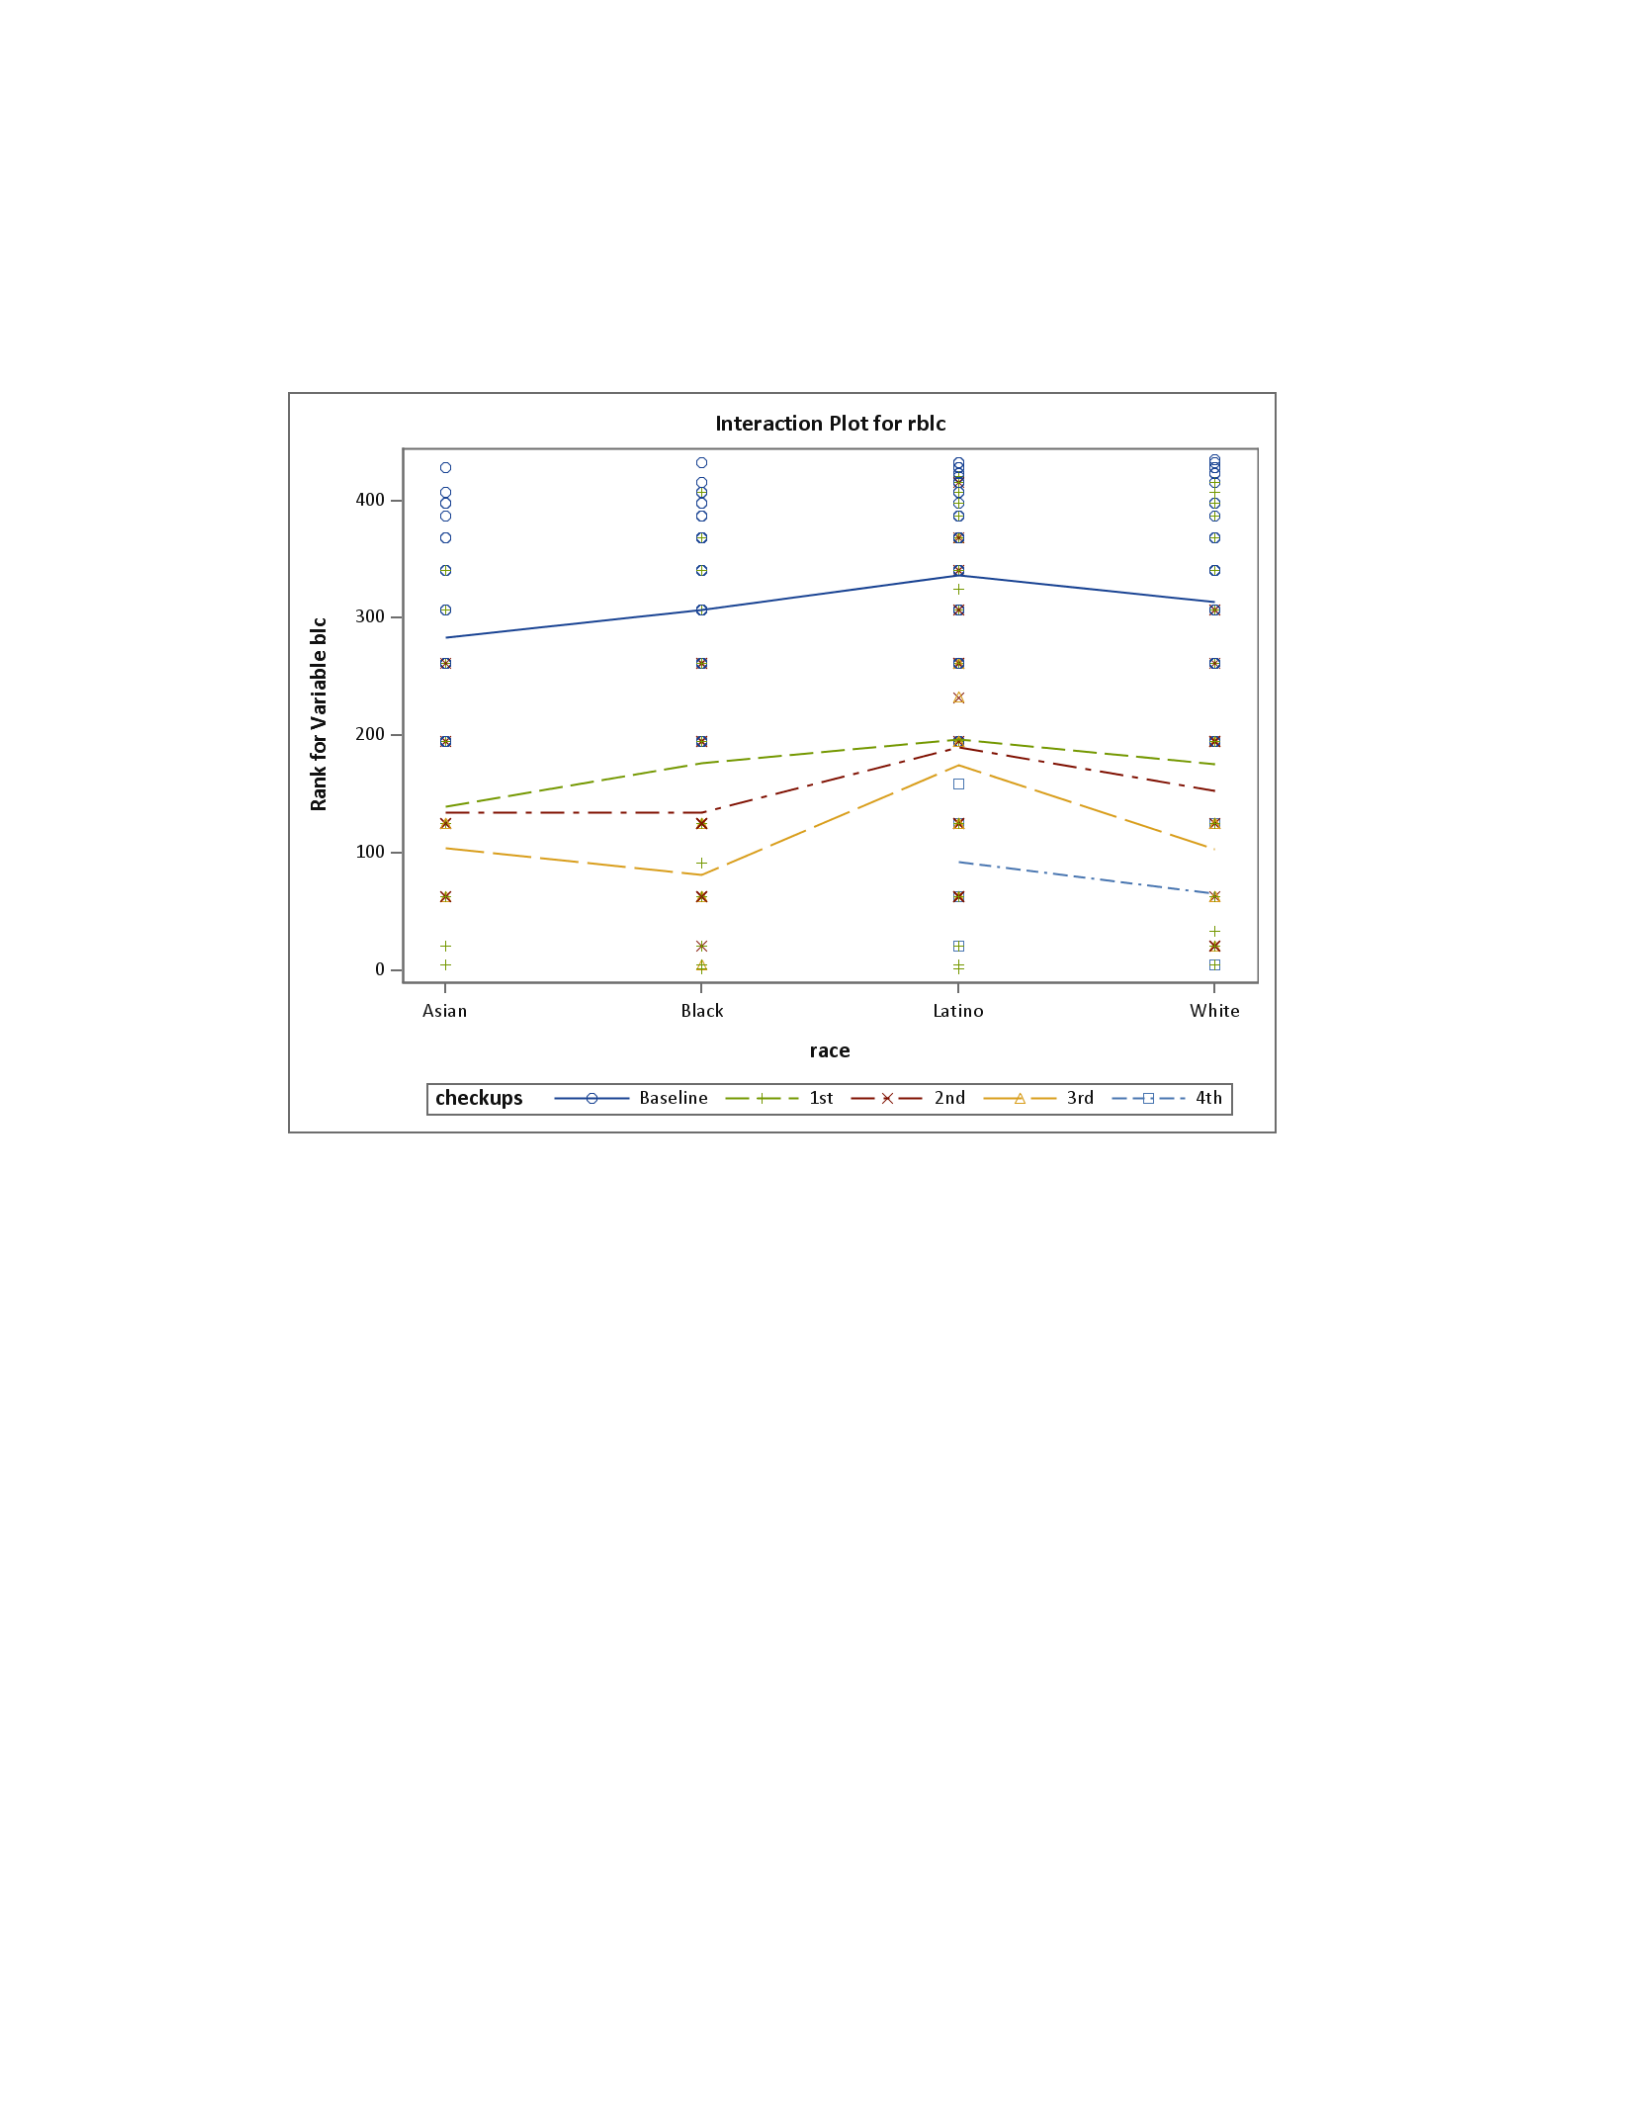
73
Figure 7
Interaction Plot Between Race and Post-Case-Management Checkup
It appears that each race group has experienced a significant drop in blood lead
content between the baseline level and the first blood check-up after case management
was initiated. However, the Latino group appears to lag behind other racial groups when
comparing blood lead reduction between 1st, 2nd, and 3rd checkups (Figure 7, Latino). In
addition, Figure 7 shows that the Latino and White groups are the only ones that reached
the 4th check-up stage before the blood content fell below the reference level of 5 µg/dL.
Interestingly, Figure 7 shows that children of Asian and Black racial groups recovered
from EBLL by their 3rd checkup.
74
Table 8
Means (µg/dL) Blood Lead Content per Race
Race
N
Mean*
SD
Latino
143
6.6a
5.5
White
102
6.1ba
3.8
Black
117
5.8ba
2.8
Asian
73
5.3b
2.5
*Mean followed by the same letter are not
statistically different
Table 8, show that the highest (6.6 µg/dL) and lowest (5.3 µg/dL) means for
blood lead content occurred in Latino and Asian groups, respectively. The blood lead
content of Whites (6.1 µg/dL) and Blacks (5.8 µg/dL) are not statistically different.
Zip Code and Case Management
Table 9
Analysis of Variance for Zip Code and Post-Case-Management Interaction
source
DF
Type III SS
Mean Squares
F value
Pr > F
zip code
2
90292.245
45146.123
4.60
0.0106
checkups
4
1764246.400
441061.600
44.92
.0001
zip code *checkups
6
32358.407
5393.068
0.55
0.770
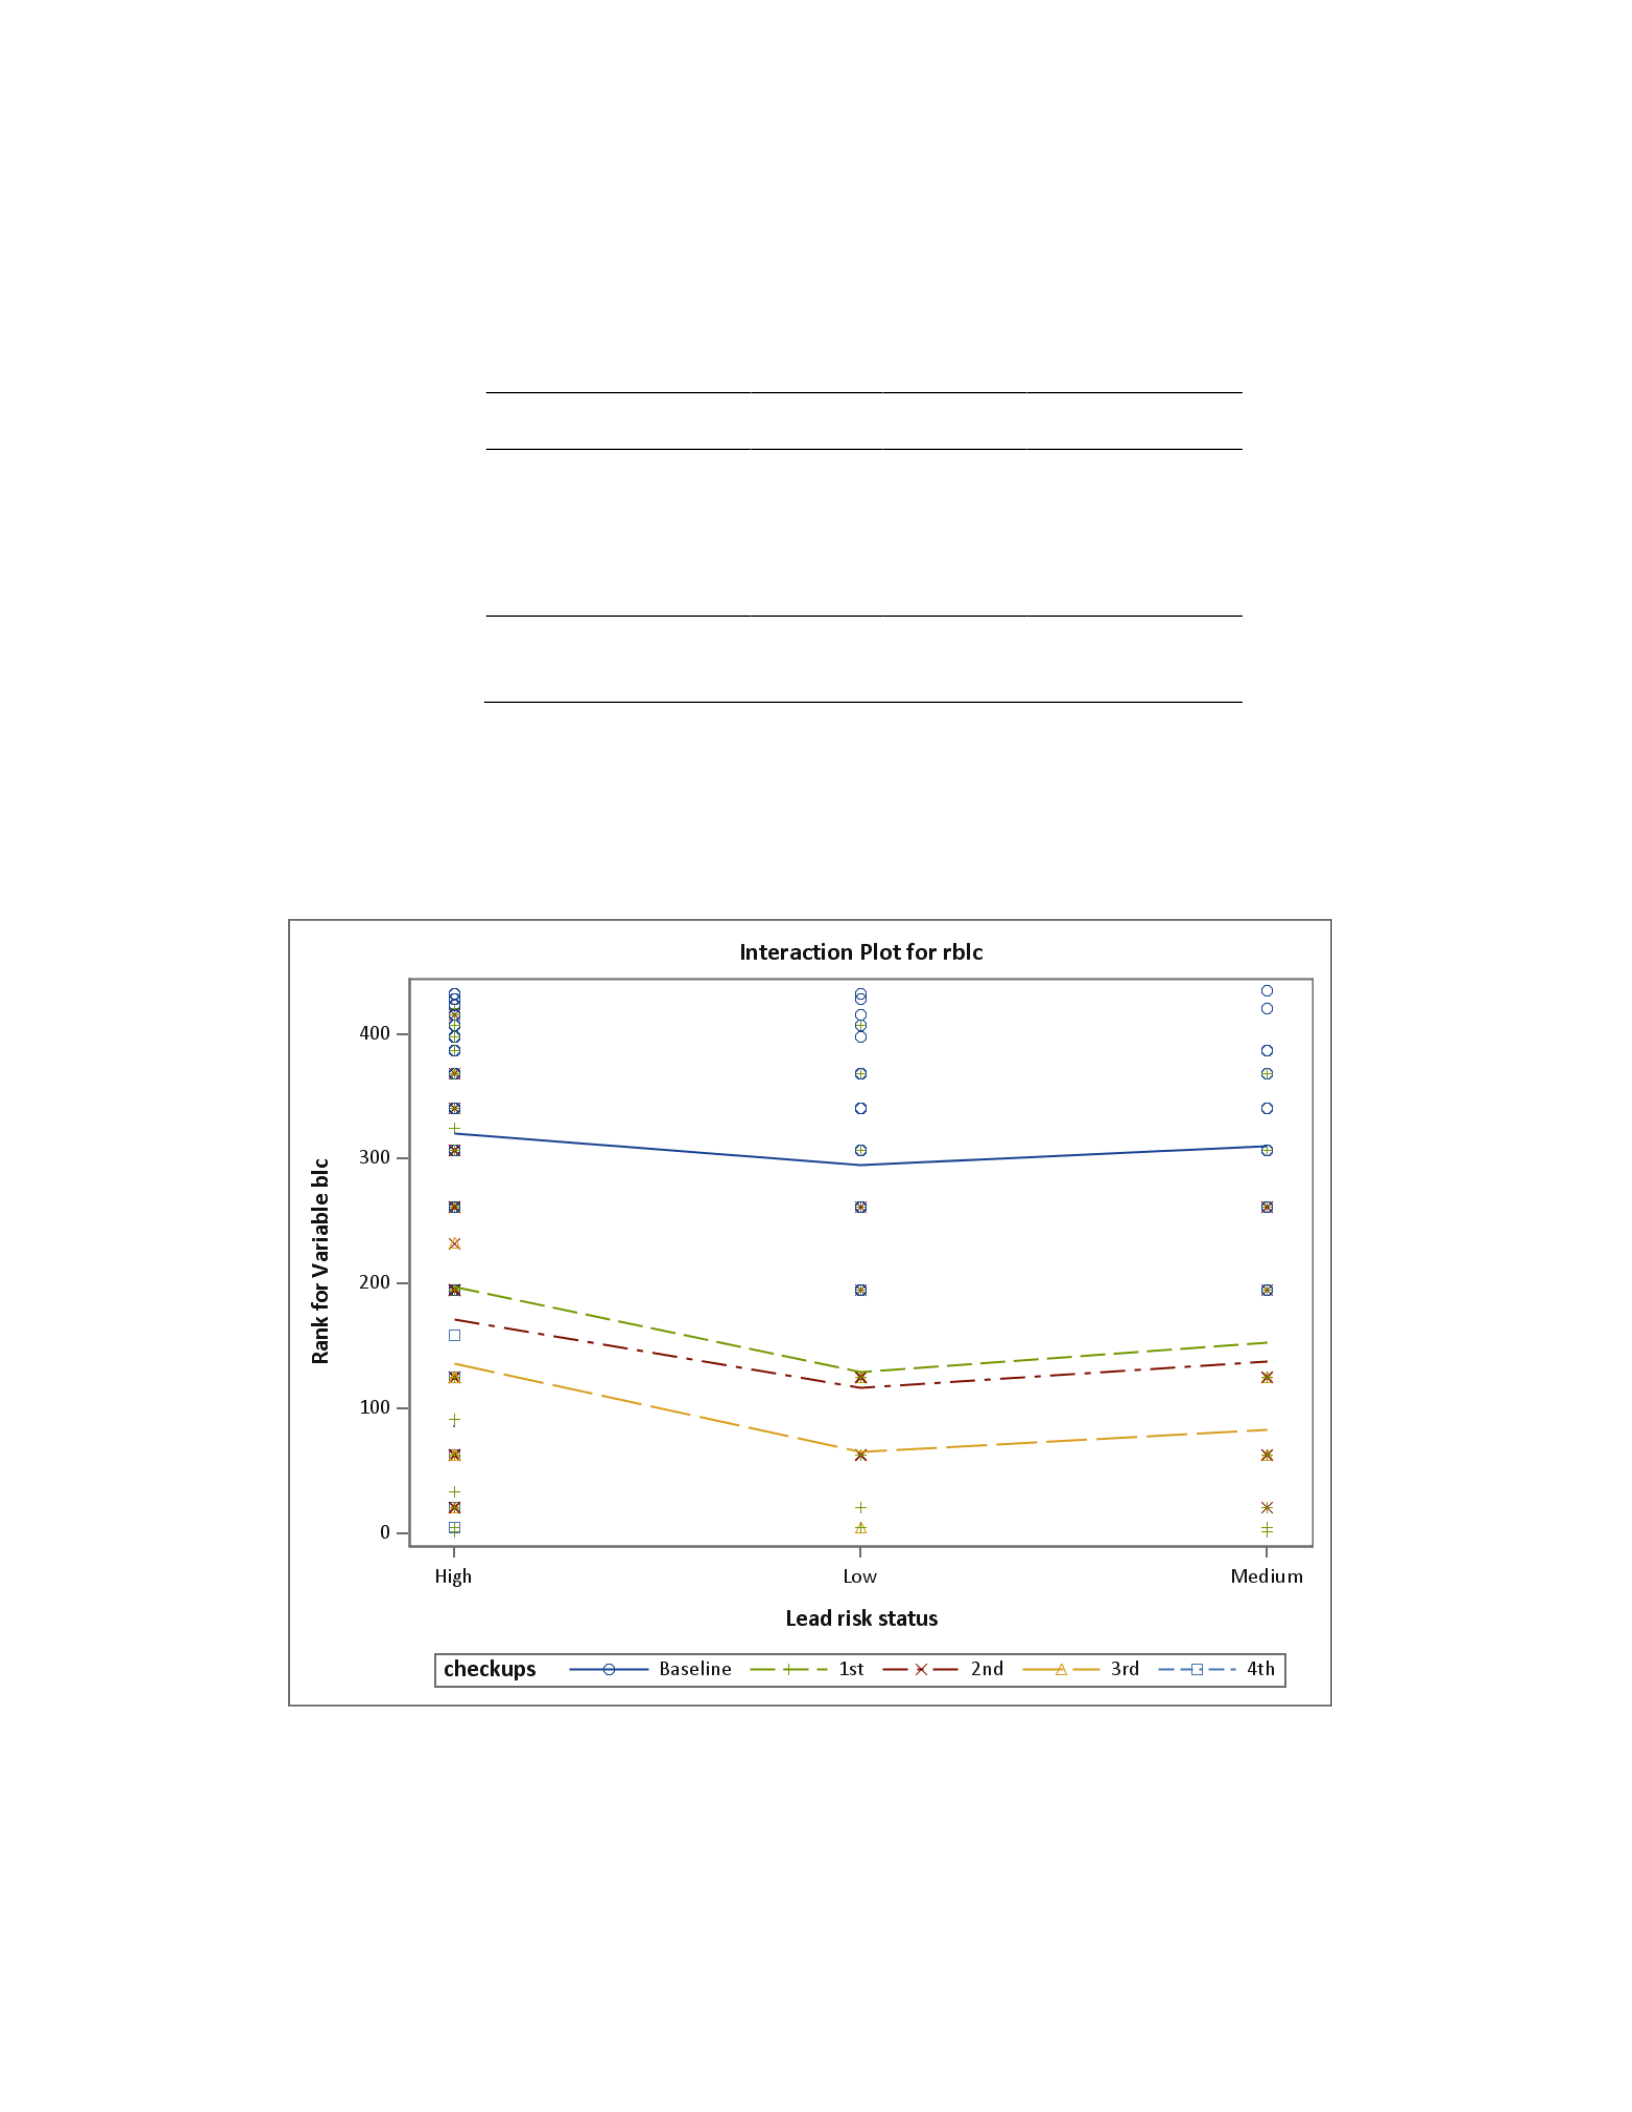
75
Table 10
Means(µg/dL) of Blood Lead Content per Zip Code Risk
Zip code
N
Mean*
SD
High lead risk
290
6.2a
3.3
Medium lead risk
54
5.7ba
3.5
Low lead risk
91
5.4b
3.0
*Mean followed by the same letter are not statistically
different
Figure 8
Interaction Plot Between Lead Risk and Post-Case-Management

76
Table 9, Figure 8, and Table 10 are about the part of Research Question Two
related to the effect of zip code lead risk status on the outcome of case management.
Table 9 shows that zip code lead risk status has a statistically significant effect on blood
lead content (f=4.60, df= 2, p > 0.01). However, there is no statistically significant
interaction between lead risk status and checkup level as shown in Figure 8. As expected,
zip codes with high lead risk levels scored the highest mean (6.2 µg/dL) blood lead level
and low lead risk zip codes have the lowest mean (5.4 µg/dL) blood contents (Table 9).
Poverty and Case Management
Table 11
Analysis of Variance for Poverty and Post-Case-Management Interaction
Source
DF
Type III SS
Mean Square
F Value
Pr > F
poverty
1
15390.684
15390.684
1.49
0.2231
checkups*poverty
8
2338926.275
292365.784
28.27
<.0001
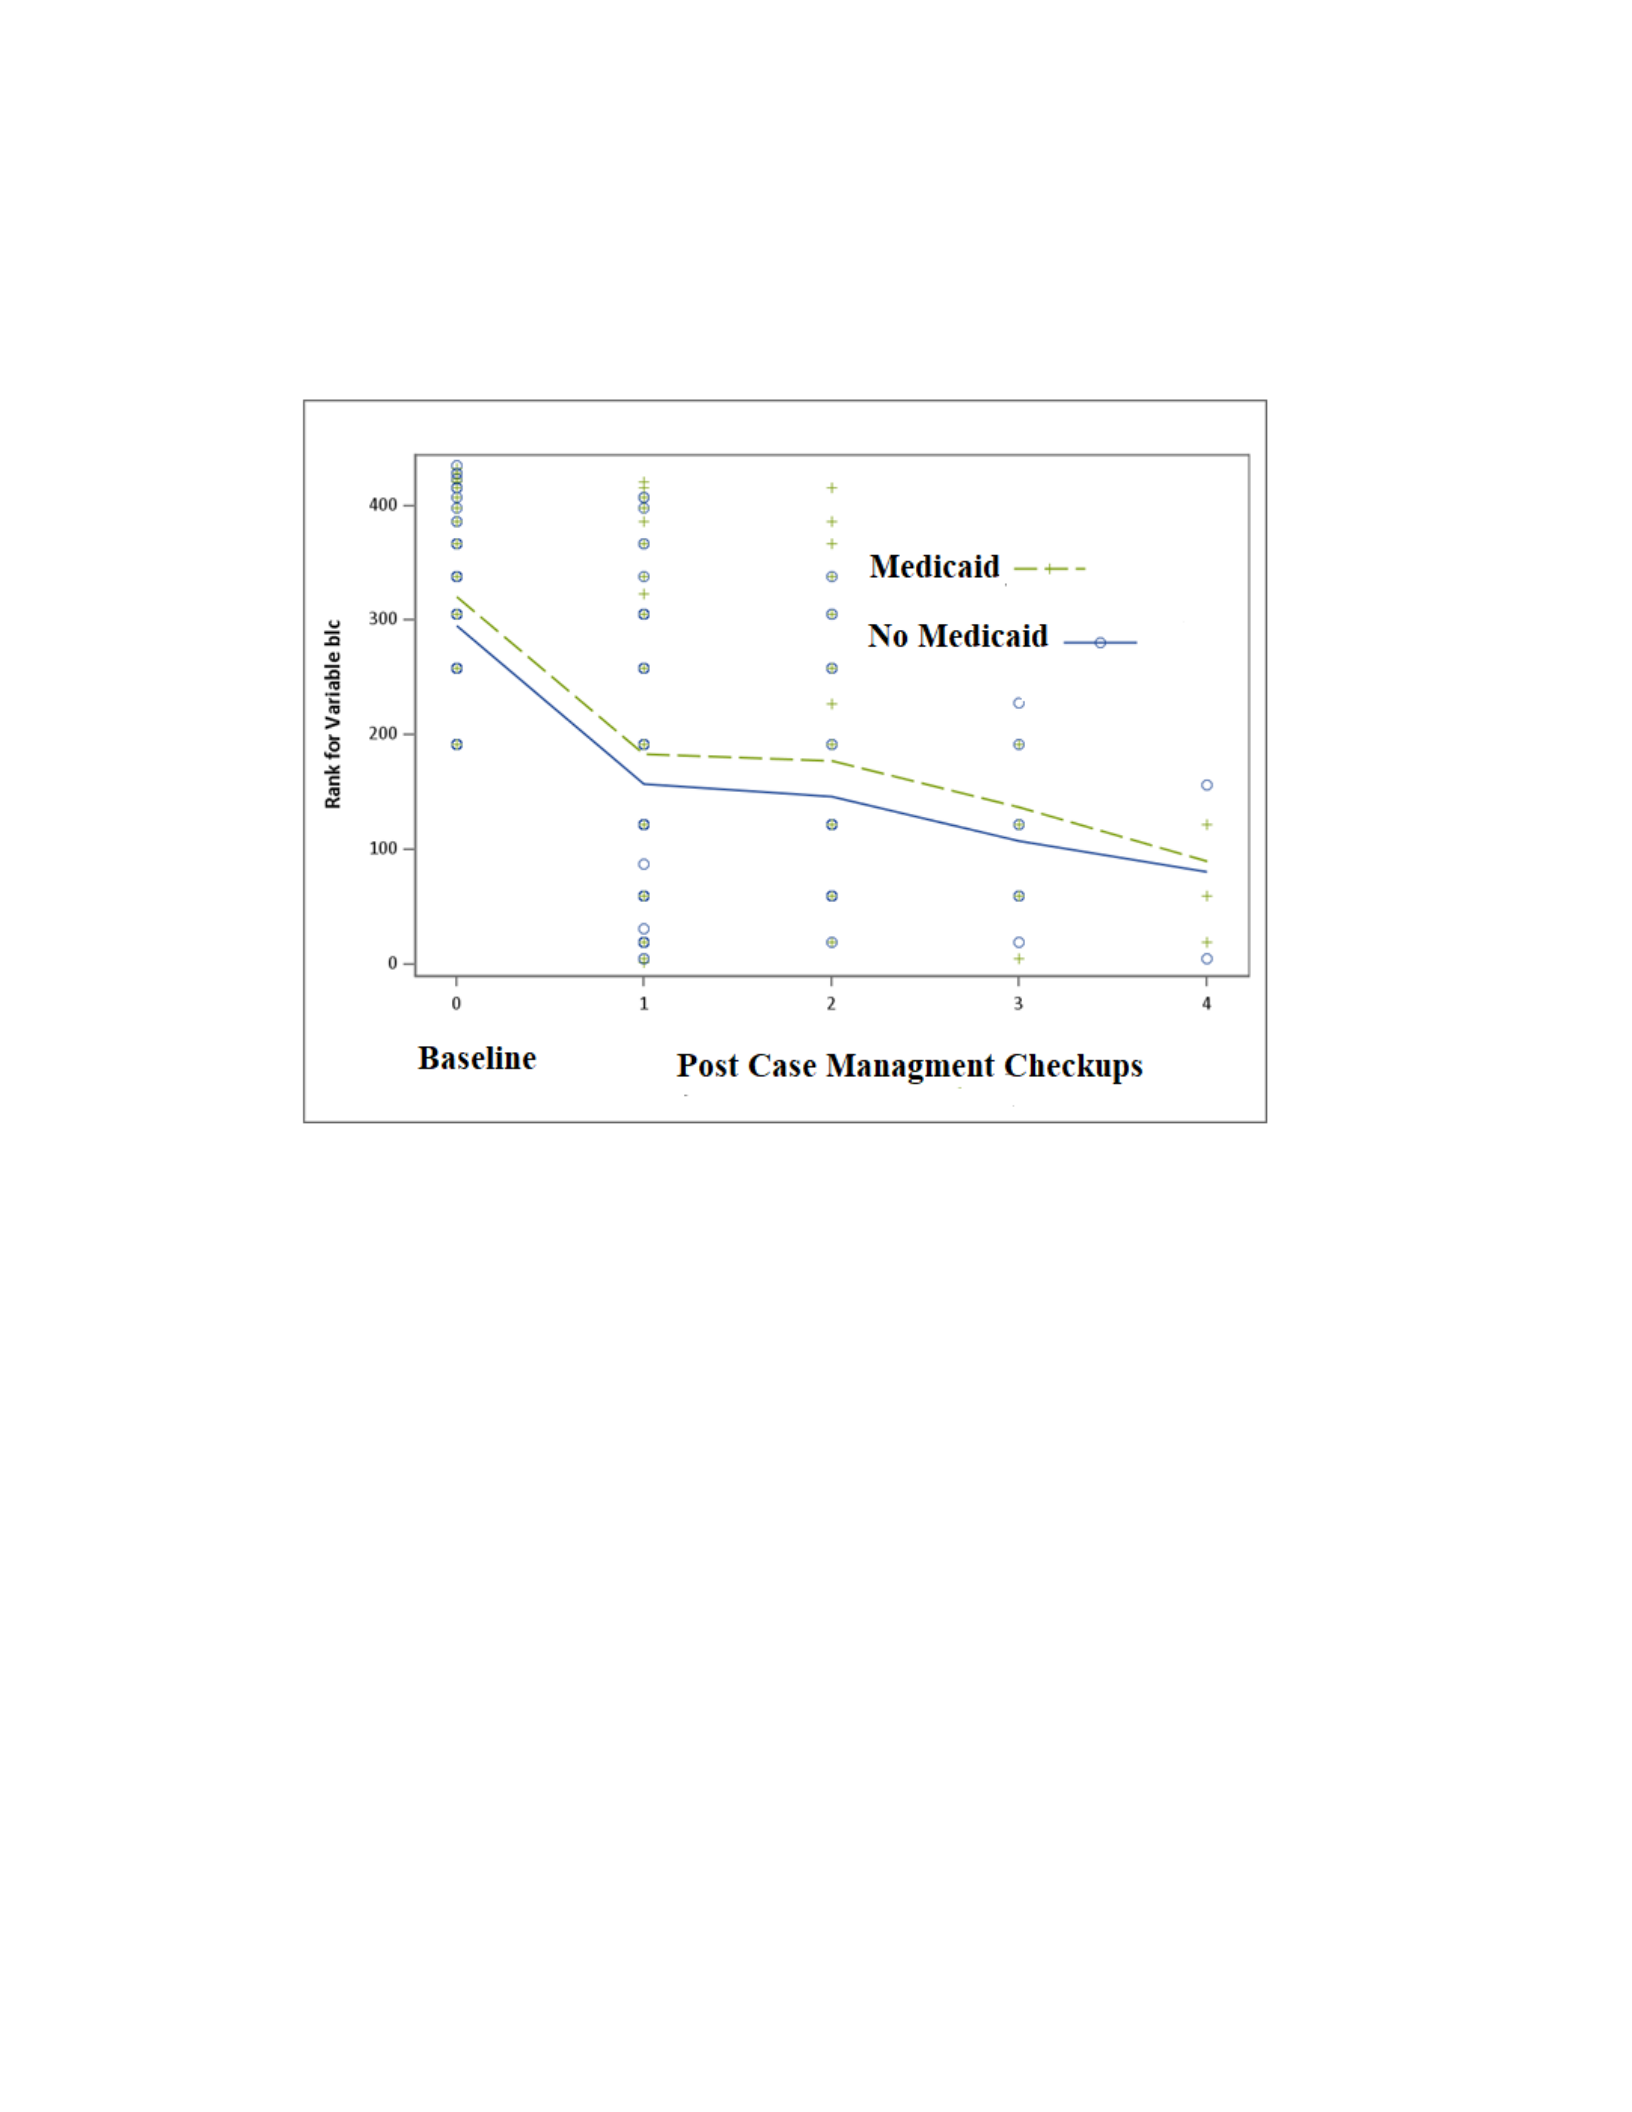
77
Figure 9
Interaction Plot Between Poverty and Post-Case-Management
Table 11 shows that there is no statistically significant difference between
Medicaid (poverty) levels. However, the interaction between Medicaid level and post
case management levels is statistically significant as shown in Table 11 (f = 28.27, df= 8,
p<.0001). Figure 9 suggests that both Medicaid eligible and the non-Medicaid eligible
group experienced a similar drop in their blood lead content between baseline and 1st
checkup. But the slope of the Medicaid eligible line between the 2nd and 4th checkup
appears to be more conspicuous compared with that of the non-Medicaid eligible line in
the same period.

78
Results of Research Question Two show that race (Table 7, Figure 7) and zip
code (Table 9, Figure 8) both affect the outcome of case management on blood lead
content, but they do not have an interaction effect on the case management outcome. In
contrast, poverty (Table 9, Figure 8) showed no significant differential effect on the mean
blood lead content but showed an interaction effect on blood lead content.
Research Question Three
The third question for this research study is: Can the difference between blood
lead content at baseline and blood lead content at post-case management time be
modified by the severity of the blood lead level at baseline? The null hypothesis (Ho) and
alternative hypothesis (Ha) for this question considering alpha = 0.05 probability level
follow
• Ho3: the difference between baseline blood content at baseline and blood level
content at post-case management time is not associated with the severity of
the lead level at baseline?
• Ha3: the difference between baseline blood content at baseline and blood level
content at post-case management time is associated with the severity of the
lead level at baseline?
To answer this question, I analyzed the data using blc as a dependent variable and
checkup as an explanatory variable while controlling for the severity of blood lead at
baseline. Here too, the analysis was carried out on the Wilcoxon rank transformed scores
because the original values were not normality distributed (Daniel & Cross, 2013; Feng et
al. 2014; Frankfort-Nachmias & Nachmias, 2008).

79
Table 12
Analysis of Variance for Severity at Baseline and Post-Case-Management
Source
DF
Type III SS
Mean Square
F Value
Pr > F
checkups
4
2427374.247
606843.562
85.67
<.0001
severity
1
639283.792
639283.792
90.25
<.0001
checkups*severity
3
67031.951
22343.984
3.15
0.0248
The result of the analysis related to Research Question Three is shown in Table 12
and Figure 10. As expected, there is significant difference between severity at baseline (f
= 90.25, df =1, p < 0.0001). More interestingly, the interaction between severity and
checkups variables are statistically significant (f = 3.15, df = 3, p <0.02). This numeric
interaction is graphically represented in Figure 10.
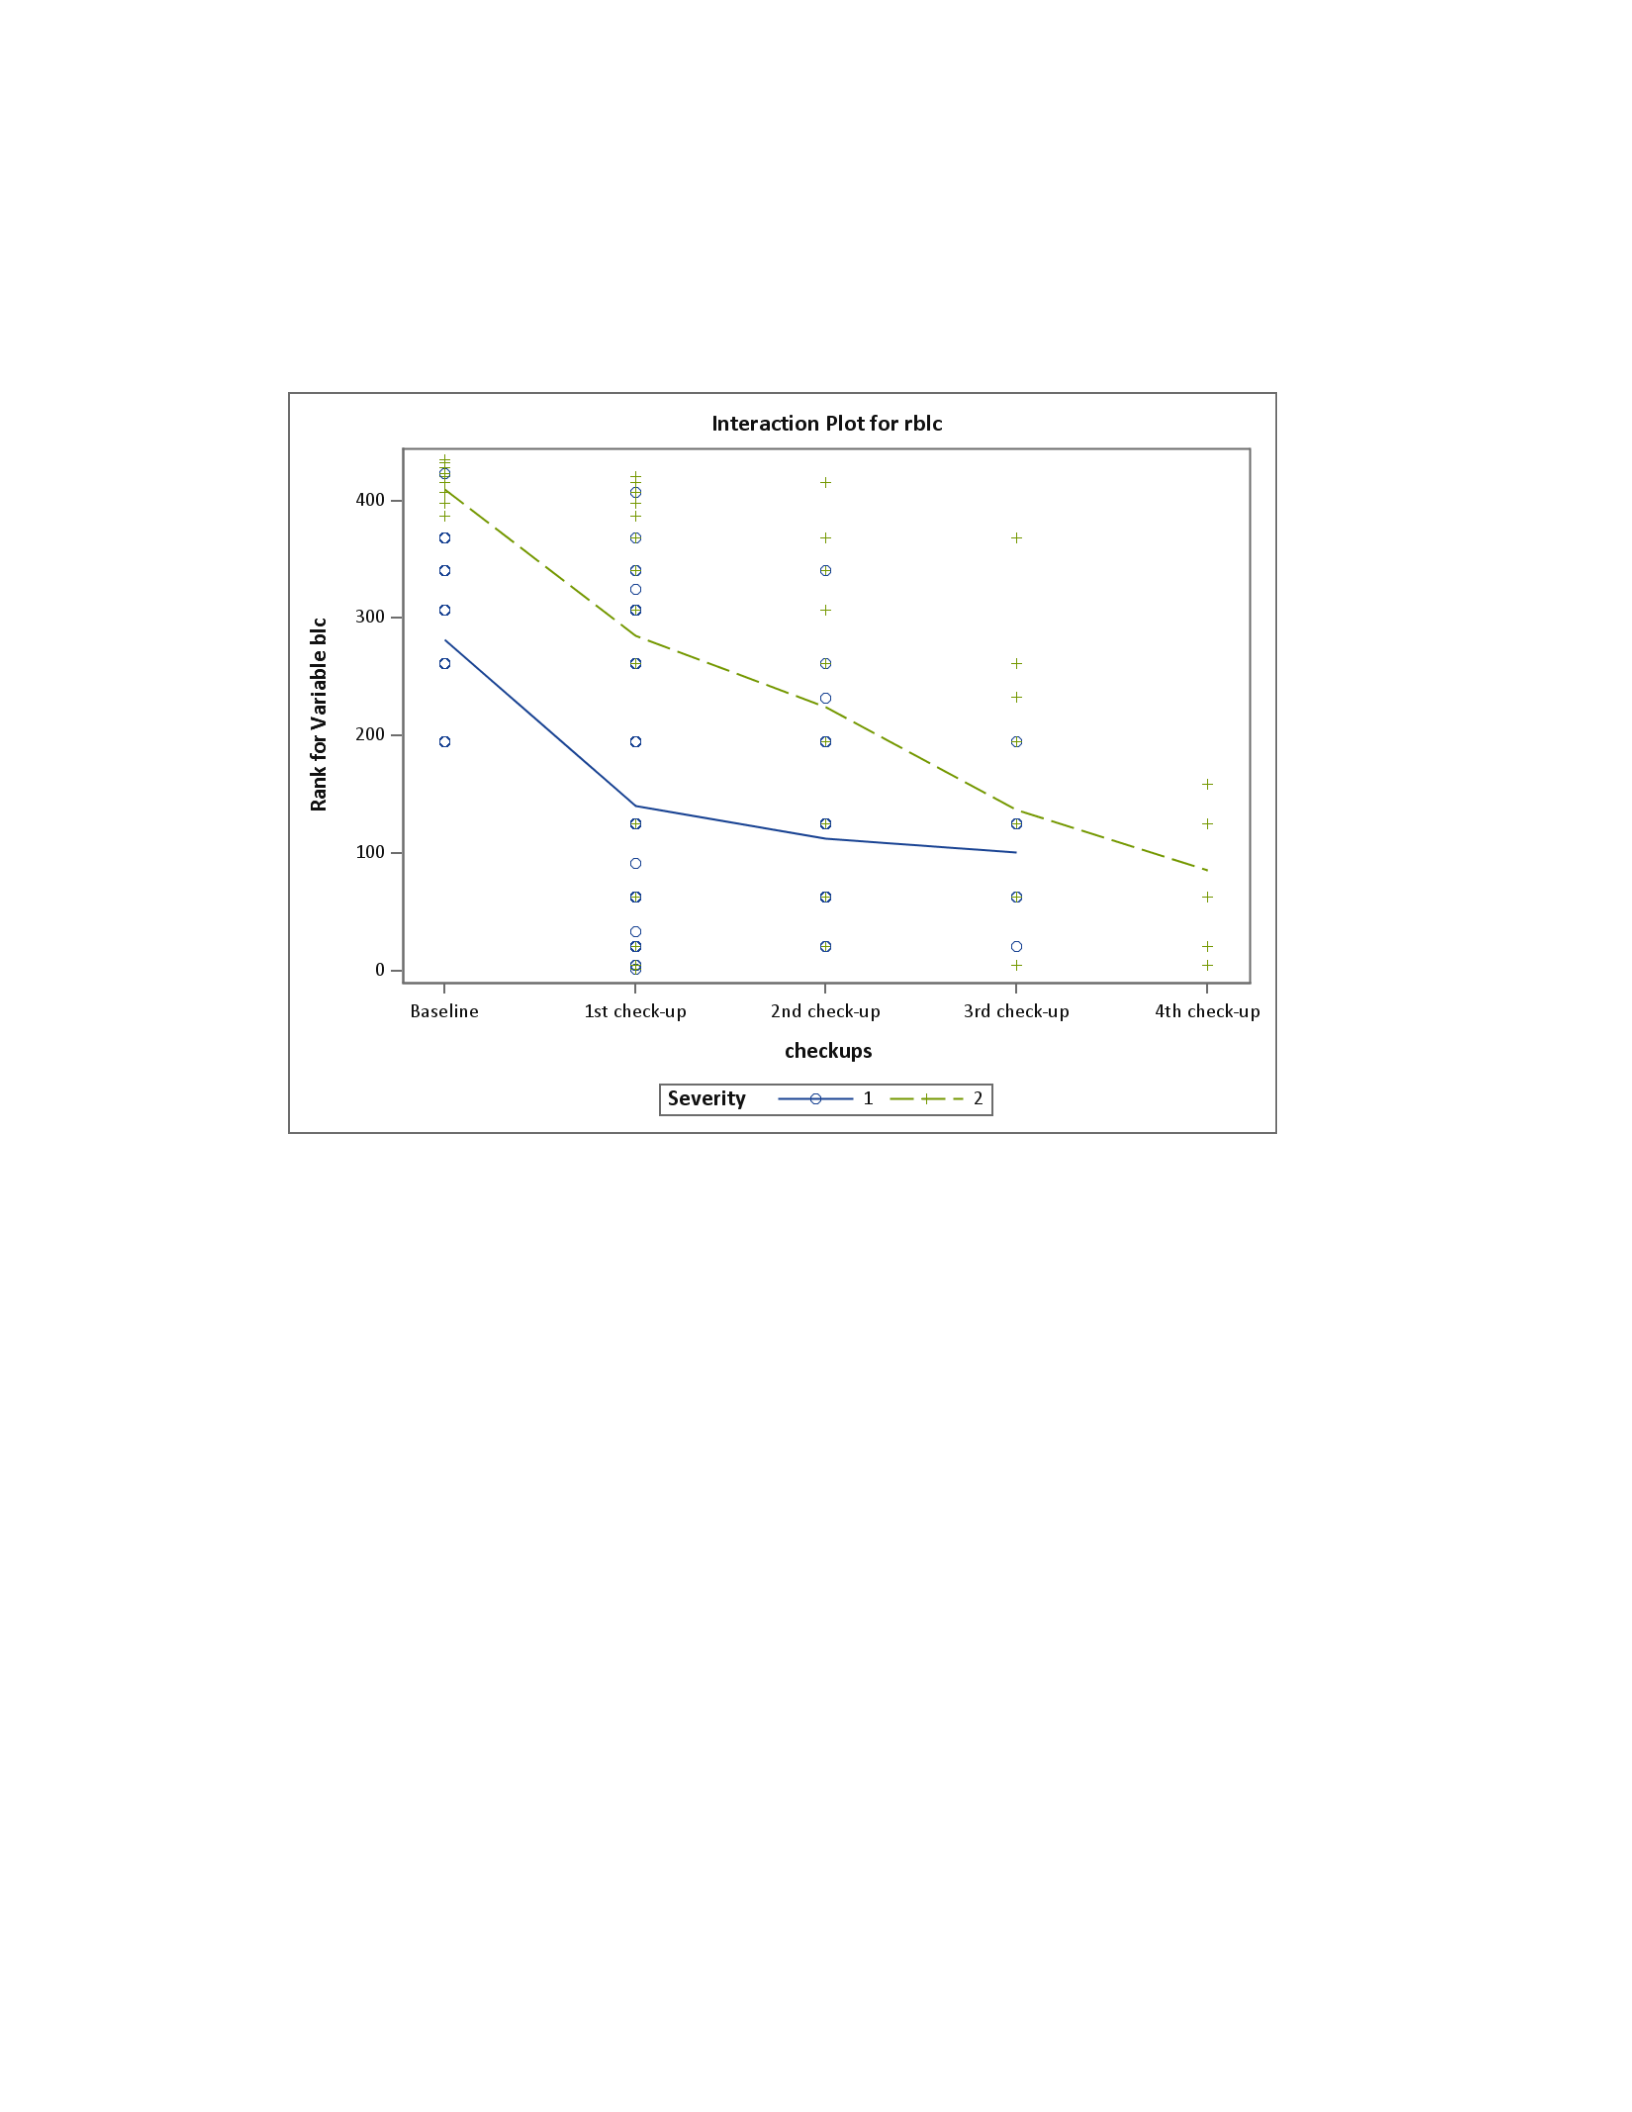
80
Figure 10
Interaction Plot Between Severity at Baseline and Post-Case-Management
Based on the statistical evidence shown in Table 12 and Figure 10, it is safe to
reject the null hypothesis (Ho) which states that the difference between baseline and post-
case management blood content is not modified by the severity of blood lead exposure
baseline. In another word, the severity of lead exposure at baseline has an impact on the
outcome of the case management.
Figure 10 shows that when the severity level is 1, the slope of the line between the
1st, 2nd, and 3rd checkup is modest. But when the severity level is 2 the slope of the line
between the 1st, 2nd, and 3rd checkup is steep. In addition, Figure 9 shows that for severity
level 1 case management follow lab test stops at the 3rd checkup while for severity level
2, case management follow labs continue to the 4th lab test. This indicates that the higher

81
the level of lead at baseline, the longer the time it takes to bring blood lead level below
the reference level of 5 µg/dL.
Summary
This chapter presents the results of the statistical analysis to answer the three
research questions. The result of research question 1 indicates that the difference in blood
lead content between baseline and post-casement time ( Checkups) is statistically
different, suggesting that case management can effectively help to bring children’s blood
level down to below the reference level of 5.0 µg/dL.
The result of the second research question indicates a statistical difference
between race groups as well as between zip codes of residence in terms of children’s
blood lead content. However, neither race nor zip code has significant interaction with
case management. The result of research question 3 shows that there is a significant
interaction between blood lead severity at baseline and case management. This suggests
the magnitude of change in blood lead content between baseline and 1st checkup is
similar for children with both severity levels. However, this magnitude tends to shrink as
the number of checkups increases.

82
Chapter 5: Discussion, Conclusions, and Recommendations
Childhood lead exposure has been associated with decreased intelligence,
behavioral difficulties, and learning problems in children (Mayans, 2019). In the United
States, childhood lead exposure has been declining since early 1979 (American Academy
of Pediatrics Council on Environmental Health, 2016; Hauptman et al., 2017). However,
many communities in the United States continue to observe a high prevalence of
childhood lead exposure. For example, in 2018 about 1.10% of children in Marion
County, Indiana, had been diagnosed with EBLL (ISDH, 2018). In Marion County,
Indiana, children diagnosed with EBLL were provided with case management services as
a public health intervention. However, no study had addressed the effectiveness of these
services for bringing children’s BLL down to below the current reference level of 5
µg/dL.
In Chapter 4, I provided statistical evidence that case management is an effective
intervention to control EBLL in children. In Chapter 4, I also showed a statistical
association between post-case-management BLL and some socioeconomic factors such
as race, zip code, and poverty. In Chapter 5, I interpret the results and provide contexts
for a better understanding of the findings. I also compare the findings of this study to
those reported by other researchers who conducted childhood lead exposure
investigations. In addition, I discuss the limitations of the study, provide some
recommendations, and describe the implications for positive social change. In the last
section of this chapter, I present some concluding remarks by summarizing the main steps
and the main finding of the study.

83
Research Question 1
The first research question of this study addressed whether case management is an
effective intervention to bring down children’s BLL below the reference level of 5 µg/dL.
Analysis of the data as shown in Table 6 indicated that the mean rank score of BLL
dropped from 311.15 at baseline to 87.94 at the fourth checkup of post-case-management
time. Moreover, Table 4 shows a significant drop in the geometric mean of BLL from 7.7
µg/dL at baseline to 3.0 µg/dL at the fourth checkup of post-case-management time.
These results provide evidence that case management was an effective intervention to
control the prevalence of childhood EBLL in Marion County, IN.
These results also support findings by Bellings and Schnepel (2018) who
analyzed the effect of case management services on elevated blood lead data of children
in North Carolina. In their study, Bellings and Schnepel evaluated the impact of case
management services using behavioral and educational outcomes, including antisocial
behaviors and school educational performance. Bellings and Schnepel reported that
antisocial behavior decreased by a 0.184 standard deviation relative to the control group.
Bellings and Schnepel also reported a significant 0.117 increase in educational
performance among children eligible for case management intervention. In the current
study, I evaluated the impact of case management services using the numeric value of
children’s blood lead content. Therefore, these two studies appear to complement each
other, and together they provide strong evidence that case management is an effective
intervention for children diagnosed with EBLL.

84
Research Question 2
Race, Ethnicity, and Case Management
The second research question of this study addressed whether the effect of case
management intervention on BLL is modifiable by socioeconomic factors such as race,
zip code, and poverty. In terms of race, Table 3 shows that 19% were Asians, 27% were
Blacks, 31% were Latinos, and 23% were Whites. Analysis of the data as shown in Table
6 indicated a significant difference between these races with Latinos having the highest
mean BLL (6.6 µg/dL), followed by Whites (6.1 µg/dL), Blacks (5.8 µg/dL), and Asians
(5.3 µg/dL), respectively.
The results in this study, therefore, suggest that Latinos are at higher risk of
childhood lead exposure compared with Asians, Blacks, and Whites in Marion County,
Indiana. However, the review of the literature indicated that these findings are not
consistent with previous findings (see CDC, 2013a; EPA, 2013), which suggests that
being Black is a risk factor but being Hispanic is not a risk factor for lead poisoning.
Findings reported by the EPA (2013a) and CDC (2013a) were observed from analysis of
national survey data, which tend to mask local level population disparities.
On the other hand, the results of the current study are consistent with the notion
that childhood lead exposure disproportionally affects the minority population as stated in
Egan et al. (2021). Latinos and Asians represented, respectively, only 10.9% and 3.8% of
the population in Marion County, Indiana (U.S. Census Bureau, 2019.). However, in the
current study, Latinos and Asians disproportionately accounted for 19% and 31% of
EBLL exposure, respectively.

85
Disparities in lead exposure can be explained by many factors including cultural
factors (Trotter, 1990; WHO, 2010). The disproportionately higher EBLL exposure level
observed in Latinos and Asians in the current study could be related to cultural and
immigration status. Lead-glazed ceramics, lead-based traditional (folk) remedies, and
contaminated spicy food have long been associated with childhood lead poisoning in
immigrant populations (Welton et al., 2018). Ritchey et al. (2011) identified Daw Tway, a
digestive folk remedy used by Burmese refugees, as a source of childhood lead exposure
in Fort Way, Indiana.
Poverty and Case Management
In the current study, 61% of the subjects were Medicaid-eligible children and
39% were non-Medicaid eligible. The high proportion of Medicaid-eligible children in
this study was consistent with the notion that living at or below the federal poverty level
is a risk factor for childhood lead exposure (CDC, 2019a). Also, Egan et al. (2021)
observed higher geometric mean BLL in children with lower socioeconomic indicators,
such as those with no health insurance, those receiving Medicaid, and those receiving
WIC assistance.
The current study also showed a significant interaction effect between poverty
and case management (f = 28.27, df = 8, p < .0001). Figure 8 shows that Medicaid
eligible and non-Medicaid-eligible children experienced similar drops in their BLLs by
the first checkup of post-case-management time (46.66% and 42.94%, respectively).
However, Medicaid-eligible children experienced significantly higher drops in their
BLLs than non-Medicaid-eligible children at the fourth checkup (34.31% and 24.67%,

86
respectively). This finding can be explained by the fact that Medicaid-eligible children
are required to have lead tests at regular intervals, and failure to conduct the lead test at
an age-appropriate time may result in loss of revenue for the health provider and loss of
insurance coverage for the family (Bruce et al., 2019).
Poverty affects childhood lead exposure in many ways such as limited access to
quality health services (Lazar & Davenport, 2018) and quality homeownership (Lynch &
Meier, 2020). Older and poorly maintained houses are well known to be potential sources
of lead exposure (HUD, 2011; Yeter et al., 2020). Housing options for Latino and
immigrants are limited to lower quality housing given their low incomes (PolicyLink,
2004).
Zip Code and Case Management
In this study, subjects were grouped in three nominal zip code levels including
High Lead Risk zip codes, Medium Lead Risk zip codes, and Low Lead Risk zip codes.
Analysis of the data showed that 63% of the subject reside in High Lead Risk zip codes,
13% reside in Medium Lead Risk zip codes and 24% reside in Low Lead Risk zip codes.
In addition, Table 8 shows a statistically significant difference between the mean BLL in
children living High Lead Risk zip codes (6.2 µg/dL) and those living in Low Lead Risk
zip codes (5.4 µg/dL). These results suggest that zip code of residence is a factor in
childhood lead exposure in Marion County, Indiana. Similar findings have been reported
elsewhere. For example, Egan et al. (2021) found that children born in Mexico
consistently had higher geometric mean BLL compared with those born in the United
States.

87
Analysis of childhood lead exposure along zip code lines is common (Gupta et al.,
2018; Kaplowitz et al., 2010). Zip code level analysis may help to identify areas or
communities for targeted interventions (Gupta et al., 2018). The use of zip code to
explain blood lead exposure, however, depends on how the risk factor is coded. For
example, data reported by Kaplowitz et al. (2010) indicated that census block is a better
predictor of blood lead prevalence than zip code if the zip code variable is dichotomized.
Research Question 3
The third research question of this study addressed whether the severity of lead
exposure at baseline has a modifying effect on the case management outcome. In this
study, the data were grouped into two severity levels: Level 1 (BLL ≤ 9 µg/dL) and Level
2 (BLL between 10 and 44 µg/dL). Analysis of the data showed that 76% of the subjects
were Severity Level 1 and 24% were Severity Level 2. In addition, the severity of lead
exposure at baseline had a significant effect on the outcome of the case management (f =
3.15, df = 3, p < 0.02). As seen in Figure 9, children in Severity Level 1 recovered from
EBLL faster (by the third checkup) than those in Severity Level 2 (not until the fourth
checkup).
These results suggest that the higher the blood level at baseline the longer the time
to recovery. Similar findings have been reported in previous studies. For example,
Roberts et al. (2001) measured the time it takes for blood lead content to decline in lead-
poisoned children following case management intervention. Roberts et al. found that
children with higher initial blood lead content take a longer time to reach below the
desired reference level of 10 µg/dL compared to children with lower initial lead levels.

88
Similar findings were also reported by Keller et al. (2017) who applied the product-limit
survival estimates to calculate the time from the first BLL ≥ 45 μg/dL until BLL declined
to ≤ 10 μg/dL among lead-exposed children in New York City.
Blood lead has a lower half-life of just about 40 days in humans (Wani et al.,
2015). Therefore, the longer time to recovery may not be solely due to high blood lead
content. For example, the AAP (2016) remarked that if the source of the exposure is not
removed from the children’s environment, BLL may continue to rise or stagnate. In the
present study, the source of lead in the children’s environment had not been recorded,
suggesting insufficient evidence to evaluate the effect of case management on the time it
takes to bring children’s BLL to below the reference level.
In another perspective, Schmidt (2017) remarked that the longer a child is
exposed to lead, the longer the decline in BLL will take. In other words, even a relatively
small BLL can take a longer time to decline if the child has been exposed to lead sources
for a longer time. The reason is that lead may accumulate in bones and subsequently be
released slowly in the bloodstream over the years (Wani et al., 2015). This can result in
persistent elevations in BLL, even in the absence of further exposure (Schmidt, 2017). In
addition, poor nutrition may also influence excretion rates. For example, iron and calcium
deficiencies are known to increase the lead in the bloodstream (Kordas, 2017).
Age and Gender
In this study, 55% of the subjects were male and 45% were female. However, the
analysis of the data showed that males and females had equal geometric BLLs of 7.7
ug/dL each. In terms of age, 5% of the subjects were < 1 year old, 80% were between the

89
ages of 1 and 3 years, and 15% were between the ages of 4 and 6 years. Analysis of the
data showed that < 1-year-old children had the highest geometric mean BLL (8.0 ug/dL),
followed by those between 1 and 3 years old (7.7 μg/dL), and those between 4 and 6
years old (7.6 μg/dL), respectively.
A 2010 EPA report indicated that, at the national level, boys had about 0.5 µg/dL
more blood lead content than girls. However, Morrison et al. (2013) reported lead study
results that showed higher average BLLs for girls compared with boys in Marion County
IN. But the results of this study showed no difference between boys and girls in term of
BLL.
In terms of age, it was previously reported that 2-year-old children tend to have
higher BLLs than 1-year-olds, probably due to mobility and hand-to-mouth behaviors
(EPA, 2013; Morrison, 2013). The results of his study, however, show that 1-year old
children had the highest geometric mean blood lead level compared with older children,
which does not support these previous findings.
Limitations of the Study
This study is designed as a retrospective cohort research. Selection and
information bias due to misclassification are obvious limitations (Howe et al., 2016).
Also, this study used a convenient sampling method. A limitation associated with this
type of sampling method is that results may not be generalizable (Jager, Putnick, &
Bornstein, 2017). The data was observational and cross-sectional, as result, the causal
relationship between variables cannot be implied. In addition, the prevalence of EBLL,

90
the disease factor, in the general population is also low and that may constitute an
additional limitation to generalize the outcome of the research (Szklo & Nieto, 2019).
This study used the HBM as a theoretical framework. HBM is mostly used to
explain the motivation of participants in disease prevention or a health promotion
program. However, in this study, no variable has been recorded to represent the
perception of parents and guardians for participating in the case management
intervention. The absence of variables to evaluate parent perception about lead exposure
and lead screening constitutes a major limitation of this study.
Parental education is an important variable for the study of childhood lead
exposure. For example, in a randomized control design, Shen et al. (2014) showed that
parental education can reduce the children’s blood lead level by up to 35%. Zhang et al.
(2013) analyzed childhood lead screening data in combination with school performance
and parental socioeconomic factors. They found that the odds ratio of having less than a
proficient score in math, science, and reading is high for children whose parents achieved
less than high school education. Another dimension of parent’s education about
childhood lead exposure can be about understanding common sources of lead, ways to
protect children from being exposed to lead, and the role of nutrition in the prevention of
childhood lead poisoning (Mayan, 2019, add another). In the present study, elements of
parent education have not been recorded, and this constitutes an additional limitation of
the present study.

91
Recommendations
Results of this study have provided statistical evidence that case management is
an effective intervention for children diagnosed with EBLL. Unfortunately, only children
with blood lead levels above 5µg/dL benefited from the beneficence of this intervention.
In addition, considering that no amount of blood lead is acceptable (Dickman, 2017,
Mayan 2019), a logical recommendation is to lower the reference level to less than
5µg/dL so that more children will benefit from case management intervention.
A similar recommendation has been proposed in previous reports. For example,
Caldwell, et al., (2017) analyzed the 2011 to 2014 National Health and Nutrition
Examination Survey (NHANES) data. They found that the 97.5th percentile
corresponded to 3.48 µg/dL which is about 30% lower than the current reference value of
5 µg/dL.
The present study is a retrospective analysis of secondary data. In a retrospective
study, the researcher does not have control of data collection. A prospective design would
allow the researcher to collect all necessary data for the study (Euser et al., 2009; Song &
Chung, 2010). For example, in this study important variable such as parental education
has not been collected and that limit the interpretation of the data. In addition, no
variables to assess parental perception about lead exposure were collected. A prospective
design would allow the researcher to collect additional usage data to enrich the
interpretation of the findings (Euser et al., 2009; Song & Chung, 2010). Therefore, I
would recommend further research on this topic using a retrospective design approach.

92
Implications
Positive Social Change at the Organizational Level
The findings of this study can be used by the local public health authorities to
make evidence-based decisions on resource allocation for the prevention and mitigation
of childhood lead poisoning. For example, these findings suggest that the majority of
children with EBLL are Latinos (49%) and Asians (30%), therefore more resources,
including for example hiring more culturally competent case managers, should be
directed toward those communities to curve the prevalence and incidence of EBLL.
Another implication of this study is to devise targeted outreach programs to
educate those communities about the risk factor of lead exposure. For example, about
20,000 ethnic Chin communities from Southeast Asian country Burma live on the south
side of Indianapolis. To reach this community, lead prevention education material such as
flyers and posters must be translated into Chin and Burmese languages (Salaz, &
Raymer, 2020).
Positive Social Change at the Individual level
This study can bring positive social change in two ways. First, it was widely
reported that Black children are the most affected by childhood lead exposure. This study
brings a social change in that it provides statistical evidence that Latinos and Asians, not
Blacks, are the most affected by lead exposure in Marion, County, IN. This may change
the public health authority’s approach to lead prevention activities in the community.
Second, communicating these results to the members of the Latino and Asian
communities will increase awareness about the negative impact of lead on children. This

93
can bring a social change in the form of change in behavior to protect children from lead
exposure.
Conclusion
In this study I analyzed lead exposure screening data collected between January
2018 and December 2019 to answer three research questions including: 1) Is there a
difference between blood level at baseline and blood lead level at post-case management
time? 2) Is the change in blood lead content between baseline and post case management
time associated with race, zip code lead risk status, or poverty? and 3) Can the difference
between blood lead content at baseline and blood lead content at post-case management
time be modified by the severity of the blood lead level at baseline?
Analysis of the data revealed that case management is an effective intervention to
bringing children’s blood lead level below the reference level because there was a
statistically significant difference between blood lead level at baseline and blood lead
level at post casement time. Also, all the socioeconomic variables tested, including race,
zip code, and poverty had a statistically significant effect on the outcome of case
management. However, only the poverty variable showed a statistically significant
interaction with case management levels.
As expected, the higher the severity of lead exposure at baseline the longer it
takes to bring the blood lead below the reference level. also, children from zip codes with
high lead risk status and those eligible for Medicaid were most exposed to EBLL. The
analysis of the data revealed that minority races including Latinos and Asians were the
most exposed to EBLL. However, there was no difference between boys and girls in

94
terms of exposure, but the younger age group (< 1-year-old) had the highest median
blood lead content compared with other age groups.
These results have important implications for the local public health authorities
because the result shows the need to direct more resources to communities that were most
affected by EBLL. The results of this study also add support to the call to the CDC to
bring the reference level of childhood blood exposure to below the current level of
5µg/dL. However, this study has some limitations that need to be considered when using
the findings. For example, the data were observational and cross-sectional, as result, a
causal relationship between variables cannot be implied. Also, due to the convenient
sample approach, selection, and information bias due to misclassification may limit the
generalizability of the findings.

