


Introduction Research in organizational communication
Research in organizational communication has demonstrated that change efforts
are difficult and disruptive. Studies have shown that for a change effort to be successful,
communication is necessary, and that communication must be strategic and allow for both
one-way and two-way communication. It has been shown that including both forms of
communication gives employees the means through which to gather the necessary
information to reduce the uncertainty that accompanies change (Kramer, 2004). This is
because with change comes an upheaval of routine. “Organizational actors
overwhelmingly favor familiar routines derived from past experience … to vague,
uncertain visions of the future” (Ford, 2001, 636). When left unchecked this uncertainty
builds into anxiety, which results in resistance (Kramer, 2004).
Communication studies have shown that in times of change, anxieties arise, but
many of these research studies focus on change efforts that involve company downsizing.
These change efforts are expected to generate anxiety because they disrupt more than
everyday work routines; they also result in a disruption of employee livelihood. In these
instances, a lack of proper communication between an organization and its employees
regarding the change effort resulted in a drop in employee morale, yet another obstacle to
overcome during an already strenuous time.
Other studies have shown that nearly all change efforts are met with resistance,
some less so than others, depending on the severity of the change and its implications for
affected employees. For example, a change in organizational procedures is expected to
meet less resistance and generate less anxiety than a change that calls for downsizing.
This is because the former implies a need to learn something new and adjust a work
routine, while the latter threatens other aspects of the employee’s life.

“Human beings do not resist change automatically; however many people do
resist being changed [or] having changes imposed on them” (Lorenzi & Riley, 2000,
117).
Organizational change normally involves some threat, real or perceived, of
personal loss for those involved. This thread may vary from job security to
simply the disruption of an established routine. Furthermore, there may be
trade offs between the long and short run. As an individual, I may clearly
perceive that a particular proposed change, in the long run, is in my own
best interests, and I may be very interested in seeing in happen, yet I may
have short-run concerns that lead me to oppose particular aspects of the
change or even the entire change project (Lorenzi & Riley, 2000, 117).
Diffusion of innovations theory of mass communications postulates that change
efforts possess characteristics that make them more likely to be accepted, and that
communication is essential to facilitate the understanding and realization of those
characteristics for an innovation to go from an abstract concept to an accepted and
adopted solution (Rogers, 1995).
This research will study the effectiveness of a communication effort at a Florida
medical facility for the acceptance and adoption of an innovation. It uses a survey
approach to measure the dissonance and disruption of a new technology and whether its
adoption is facilitated through the use of communication. It seeks to find a link among
resistance, anxiety, and understanding and will use organizational change theory,
uncertainty reduction theory, and aspects of diffusion of innovations theory to analyze the
results.
The medical facility is a “multidisciplinary group of physicians, surgeons, and
health care providers” (www.floridamedicalclinic.com) that brings together primary care
physicians and multi-specialty physicians in one location to provide patients with a
complete health care experience.

In the Fall of 2006, the medical facility introduced a new technology into the
everyday activities of the hospital that would affect both doctors and employees. It is the
“biggest change for most of [their] employees’ day to day activities that [the medical
facility] has ever had” (Joe Delatorre, Interview 03/30/06). The change involves
transferring the entire medical records system to a server thus becoming a paperless
facility. The innovation was launched October 24 and within the span of six months it
was expected that all departments would have changed over. The change would have
many benefits for the hospital, such as facilitating the exchange of patient records
between doctors. By going paperless, the medical facility would require employees,
especially doctors, to change the way they are accustomed to doing their jobs
significantly. Doctors would no longer have their paper charts with their patient’s medical
history. Instead, these records would be kept on a server from which doctors could share
the information and avoid performing duplicate procedures such as blood work or X-rays.
The change included adding computers to the exam rooms to allow for access to patient
charts while doctors see with their patients. This new technology was expected to save
time, money, make the overall health care experience easier for patients as well as
facilitate the everyday activities of the hospital staff.
Directors at the medical facility understood that this change was an enormous
undertaking and informed employees that the change would taking place. The
organization believed that the individuals who would pose the biggest challenge in this
change would be medical staff, particularly those who did not regularly use the computer
system was in place prior to the change effort. Other hospital employees were already
accustomed to using a system very similar to the one being implemented on a daily basis

and with the change over would only need to adjust to minor changes, such as the order
in which the system requests information.
The medical staff, on the other hand, did not use the original computer system
nearly as often, with some of the doctors not using it at all. For these individuals the
transformation was a severe change and the medical facility expected that without proper
training the change would meet a lot of resistance.
As a result, the organization conducted training programs for the medical staff.
Doctors would be divided into beginner and advanced user groups. Advanced users
would have some working knowledge of the current computer system, from already
having many of their patient files on the current server and were able to navigate through
it with ease (J. Delatorre, 03/30/06). The rest of the physicians fell into the beginner
category. The advanced users were trained and expected to use the new system by the
October 24 launch date. Physicians categorized as beginners were trained with their
departments for the later launch dates. The first group of beginner physicians began their
training in November and were expected to be ready to change over to the new system by
December 11. Because physicians are so busy, they posed a special challenge. They had
to learn the new system, but do so while still handling their regular patient load. To
accommodate this, there were four, four-hour training session offered on Saturdays.
During the span of these four hours, the physicians would be taught how to use the new
system, and would be allowed to return to any other training session if they felt they need
extra help in any particular section.
The goal of the program was to get doctors to transition from a traditional medical
documentation system to an electronic medical records system (J. Delatorre, interview
03/30/06). In doing so, the training would “get the advanced users to fully understand and

be comfortable with the new software, and get the basic users [to] an intermediate level of
familiarity with the program” (J. Delatorre, Interview 03/30/06). Ideally, doctors would
become acclimated to the program and feel comfortable using it on a daily basis,
understand the benefits that would follow its implementation, and demonstrate less
resistance to using the new technology.
The medical facility understood that users at the beginner level would likely not
reach an advanced user stage after the training program; however, the intention was to
make them feel comfortable using the new system, so they would be more inclined to
accept it and continue making strides in learning the program with daily use.
The thought behind this training program resembles many of the deductions from
organizational communications theories and mass communications theories in that the
medical facility expects that the communication and training will help in reducing
resistance to change while increasing understanding and, in turn, result in the acceptance
and adoption of the new technology. They plan to accomplish this by showing the
medical staff how to use the innovation.
This research study examined the effectiveness of the training program in familiarizing,
explaining, and adopting the new computer system among the medical staff at the Florida
medical facility within the context of organizational change and uncertainty reduction
theories.
Not unexpectedly, then, this research set out to determine the effectiveness of the
training program in increasing user knowledge of the new computer system and
understanding of its benefit, reducing user resistance and feelings of uncertainty towards
the new system and increasing acceptance and adoption of the innovation.

CHAPTER 2
Literature Review
In this day and age organizational change is inevitable. Businesses today are
fastpaced and globally minded. With the onset of globalization, advances in technology
and amount of available information, change is not an exception but a rule. Organizations
must adapt to keep up with societal trends and market demands. “As organizations
attempt to cope with a progressively more turbulent economic, technological, and social
environment, they rely increasingly on their employees to adapt to change” (Stanley, D.J.,
Meyer, J.P. & Topolnystsky, L., 2005, p. 429). Considering change is such a large and
necessary part of any organization; organizations must find ways to implement necessary
changes in the most efficient way possible.
A great deal of research has gone into the effective implementation of
organizational change. This research has indicated that implementing organizational
change is no easy feat, and it often encounters significant opposition. Change brings with
it an uprooting of routine and comfortable tasks, which results in discomfort for
organizational members.
The typical employee spends at least eight hours a day doing, in general,
fairly routine tasks… There’s a tangible agreement that if the employee does
X, and does it well and on time, the employee will receive Y in
compensation…. There is also a psychological contract between employee
and company: As long as the employee fits into work and social patters, he
or she “belongs” (Managing Change and Transition, 2003, p. 85).
Change represents a redrafting of the social and psychological agreement.
When major change must be implemented, there is a need for the organization
to acquire new attributes that often call for new norms of behavior. Members’
previous identifications, which involve cognitive, behavioral and affective
components and which were once functional, become a hindrance to the

implementation of change …. Major change implies the loss of a system of
relationships with coworkers, customers or other stakeholders, and a
particular conception of one’s work, status and role within an organization
(Chreim, 2002, p. 1123).
During times of organizational change these agreements are more difficult to meet.
Tasks change, and it is more difficult to complete work well and on time. “Change always
requires the effort to learn the new, which is a loss in terms of time and energy that could
have been used elsewhere” (Lorenzi & Riley, 2000, p. 120). This results in social changes
that leave organizational members feeling out of place. Individuals seek out this
identification because “it provides the possibility of inclusion in social groups ….
Member identification satisfies a number of individual needs including needs for safety,
affiliation, self-enhancement and meaning in one’s life” (Cherim, 2002, p. 1120).
Changes can cause feelings of anxiety and loss, and are the reasons attributed to the
resistance organizations face during periods of change (Managing Change and Transition,
2003).
Feelings of anxiety and loss are a result of uncertainty. “Giving up familiar
attitudes, behaviors and perspectives that emanate form one’s identifications opens the
possibility for the uncertain and creates fear of the unknown, leading people to hold on to
past identifications” (Chreim, 2002, p.1123). Organizations must find effective ways to
reduce uncertainty, anxiety, and feelings of loss in order to reduce resistance, and as a
result, effectively implement a change effort. It is necessary to provide meaning and
background to change, so that organizational members are once again able to identify
with the organization. Communication provides the opportunity to furnish meaning
(Cherim, 2002). Research has indicated that communication is necessary in any effective
change effort (Managing Change and Transition, 2003).

Communication is an effective tool for motivating employees, for
overcoming resistance to an initiative, for preparing people for the pluses
and minuses of change, and for giving employees a personal stake in the
process. Effective communication can set the tone for a change program
and is critical to implementation from the very start” (Managing Change
and Transition, 2003, p. 60).
Unfortunately, this seemingly simple solution is “often used poorly or
thoughtlessly” (D’Aprix, 1996, p. 3). It is necessary to have a powerful rationale to
help reduce or fight the cynicism that results from uncertainty and confusion
(D’Aprix, 1996). If communication is not used properly, it can worsen the situation.
For example, research indicates that “when personal experiences contradict
persuasive efforts by [an] organization, the latter’s discourse is ignored and
members will rely on their past experiences to guide their interpretations”
(Chreim, 2002, p. 1133).
To be effective, communication should be strategic. Strategic communication
is “a process by which…an organization deliberately manages its communication
proactively…” (D’Aprix, 1996, p.5). Strategic communication requires planning and
forward thinking. This is not to say that all communication efforts must be planned
and scripted, but for an organization to be aptly prepared, its members and
communicators must have a clear understanding of what to expect.
Communication and Uncertainty Reduction
As discussed earlier, uncertainty is the primary cause associated with change
resistance. “Because organizational change by its very nature is not linear, the most
frequent psychological state resulting form organizational change is uncertainty (
Jimmieson, N.L., Terry, D.J & Callahan, V.J., 2004, p. 11). Uncertainty reduction theory,
a formal communication theory, “attempts to explain human communication behaviors in

uncertain situations” (Kramer, 2004, p.4). Uncertainty is a fundamental experience. On an
average day most adults spend their time in groups and organizational settings more than
in any other activity. Understanding how they manage uncertainty is of grave importance.
Jimmieson et al (2004) talk about the different kinds of uncertainty associated with
organizational change. Those include role conflict, role ambiguity, and role overload.
Individuals experience role conflict when role expectations after a change are in direct
opposition to past expectations. Likewise, role ambiguity happens when old expectations
are not replaced with new, clear-cut expectations. Additionally, “employees may
experience role overload when too many tasks are assigned in a given time period or
when new job duties go beyond employees’ current knowledge skills, and abilities” (p.
11).
To ensure that change programs minimize uncertainty, information exchange is
crucial. “When profound organizational change is imminent, employees go through a
process of sense-making, in which they need information to help them establish a sense
of prediction and understanding of the situation” (Jimmieson et. al., p. 12). Generally,
“when individuals feel that they are receiving insufficient information, they experience
uncertainty and as a result dissatisfaction. Conversely, when they feel they are receiving
sufficient information, they experience certainty and as a result will experience
satisfaction and confidence in their organizational roles” (Kramer, 2004, p. 42). This is of
concern to organizations because with dissatisfaction comes various problems, namely,
low productivity and employee turnover. Therefore, during times of change it is vital to
communicate with employees every step of the way. Otherwise, employees will seek to
subdue their fears by searching for information elsewhere. This is a particularly

dangerous alternative because the information they will rely on will likely be based on
speculation and half truths.
If employees can not receive information from formal sources they will turn to
informal sources, such as the grapevine or rumor mill. Unfortunately, these informal
sources can carry with them incomplete information or incorrect information that may
increase anxiety (Kramer, 2003).
Results from research examining how individuals manage uncertainty as a
result of organizational change are fairly consistent… Due to a lack of
adequate information surrounding organizational changes, organizational
members experience uncertainty. The uncertainty frequently leads to
dissatisfaction and intentions to leave. Additional communication with
organizational supervisors or other members results in uncertainty reduction
and more positive feelings toward the organization and intentions to remain
in the organization (Kramer, 2004, p. 55).
One can conclude, then, that uncertainty reduction theory demonstrates the
need for internal communication in an organization, especially during times of
change.
Communication leads to understanding, understanding reduces uncertainty,
and as a result reduces resistance. But how does this sequence of events take place?
What makes communication effective? What kind of communication is necessary to
reduce uncertainty, reduce resistance, and ensure successful implementation of
change programs?
The diffusion of innovations theory of mass communications takes a look at how
innovations are accepted by groups and individuals and the strategic communication
necessary to achieve this acceptance.
Diffusion of Innovations: Theories of Mass Communications Diffusion of
innovations theory of mass communication provides a theoretical framework for the

adoption of new ideas by individuals or members of a social system. It evolved from the
two-step flow model (Severin & Tankard, 2001). According to diffusion of innovations,
an innovation is “an idea, practice or object that is perceived new by an individual or
other unit of adoption” (Rogers, 1995, p. 11). Diffusion of innovations, then, is “a social
process in which subjectively perceived information about a new idea is communicated.
The meaning of an innovation is thus gradually worked out through a process of social
construction” (Severin & Tankard, p. 208).
It is important to note that this theory takes into account the uncertainty that
innovations and technologies bring with them. As mentioned, uncertainty is the primary
motivator for resistance to change. Diffusion of innovations postulates that “an
innovation generates a kind of uncertainty in that it provides an alternative to present
methods or ideas…” (p. 208) An innovation’s rate of adoption is affected by the degree to
which adopters view the innovation as having relative advantage, trialability,
observability, and reduced complexity.
Rate of Adoptionon
Innovations possess characteristics that affect the rate at which they are accepted
and adopted. These characteristics are based on the “perceptions of the innovation,
characteristics of the people who adopt the innovation, or fail to do so; and contextual
factors, especially involving communication, incentives, leadership, and management”
(Berwick, 2003, p. 1970).
Both Rogers (1995) and Berwick (2003) postulate that between 49 and 87 percent
of variance in the rate of adoption can be attributed to the perceptions individuals have
regarding an innovation. Rogers referred to these as: relative advantage, compatibility,
complexity, trialability, and observability.

Relative advantage refers to the “degree to which an innovation is perceived as
better than the idea it supersedes” (Rogers, 1995, p. 15). Relative advantage can be
measured according to various terms. It is, essentially, the perceived benefit of the
change. “Individuals are more likely to adopt an innovation if they think it will help
them” (Berwick, 2003, p. 1971). It can have economic advantage, social prestige,
convenience, and satisfaction, among others (Rogers, 1995). The more advantage is
perceived, the more useful the innovation is considered.
This idea is a more complicated idea than it appears … because for most
people who accept or reject an innovation, benefit is a relative matter – a
matter of the balance between risks and gains and of risk aversion in
comparing the known status quo with the unknown future if the innovation
is adopted. The relative calculation of value involves risk and benefit. The
more knowledge individuals can gain about the expected consequences of
an innovation … the more likely they are to adopt it (Berwick, 2003, p.
1971).
Another aspect that assists in the diffusion of an innovation is its compatibility.
This refers to the “degree to which [it] is perceived as being consistent with the existing
values, past experiences and [current] needs of potential adopters” (Rogers, 1995, p. 15).
In other words, a change must resonate with the perceived needs and belief systems of an
individual or organization (Berwick, 2003). The more an innovation strays from the
values of an individual or an organization the more challenging its adoption. “The
adoption of an incompatible innovation often requires the prior adoption of a new value
system,” this is a relatively slow process and it is important to know ahead of time if such
an undertaking is in the works (Rogers, 1995, p. 16).
An innovation’s complexity refers to how difficult it is to understand and use
(Rogers, 1995). “Generally, simple innovations spread faster than complicated ones”
(Berwick, 2003). “Some innovations are readily understood by members of a social

system,” these will be adopted more easily than those that are more complicated (Rogers,
1995, p. 16). Familiarity and understanding reduce uncertainty. As discussed, the less
uncertainty an innovation creates the less resistance it will meet. This makes
understanding a key component in the adoption of an innovation.
Giving individuals the opportunity to experiment with an innovation can
positively affect adoption. This experimentation is referred to as trialability. In
organizations, it is sometimes wise to implement change processes on a trial basis in one
department to see how successful the innovation will be. If the innovation is successful
within that department, its success can be used as a reason to adopt it throughout the
organization. Trialability and observability are closely connected. If the results of an
innovation are visible to other individuals, and considered positive, those individuals are
more likely to adopt it (Rogers, 1995).
To successfully implement any change effort, organizational leaders must
understand how these characteristics apply to their specific change effort. This way,
communication efforts can be specifically tailored to focus on the areas of change that
will encounter the most resistance. For example, a change efforts’ relative advantage may
be easy to see; however it may be a complex change. Communication should be
concentrated on the change efforts’ complexity more than on its relative advantage.
Employing change agents to diffuse information
Communication is an essential part of the diffusion of innovations theory; it is,
after all, a mass communications theory. “Diffusion is a particular type of communication
in which the message content that is exchanged is concerned with a new idea. The
essence of the diffusion process is the information exchange” (Rogers, p.17). Considering

that organizational change efforts are forms of innovation, then communication is also
essential in successfully implementing a change program.
As mentioned earlier, the diffusion of innovations theory evolved from the
twostep flow theory of mass communications. The two-step flow model uses opinion
leaders as communication agents because of the influence they have on message
receivers. According to the two-step flow theory, “influences stemming from the mass
media first reach ‘opinion leaders’, who, in turn, pass on what they read and hear to their
every-day associates for whom they are influential” (Katz, 1957, p. 61). In the two-step
flow theory, communication usually takes place between homophilous individuals
(Severin & Tankard, 2001). “Homophily is the degree to which two or more individuals
who interact are similar in certain attributes” (Rogers, 1995, p. 19).
It should come as no surprise that diffusion of innovations also takes into account
the influence that change agents have in the adoption of a new idea. However, unlike in
two-step flow, “one of the most distinctive problems in the diffusion of innovations is that
the participants are usually quite heterophilous” (Rogers, p.19). Generally, change agents
or “early adopters” (Berwick, 2003, p. 1972) are more technically savvy than the
individuals with whom they are communicating. In the case of organizational change, the
communications specialist is usually more informed about what is taking place with the
change program than the employees he or she is communicating with. Also, it is common
in many organizations for decision making to come from above and filter down through
the organization. As a result, the individuals affected and adopting the change are
inherently different from those imposing or communicating the change. “This difference
frequently leads to ineffective communication as the participants do not talk the same
language” (Rogers, p.19). To overcome the heterophily, change agents often employ the

use of aides “recruited from the local population” for a more successful communication
process (Severin & Tankard, 2001, p.211). These aides, often referred to as change
agents, are typically, well connected socially, and, watched among the “early majority”
(Berwick, 2003, p. 1972). The early majority, the first wave of individuals to which an
innovation is diffused, “learn mainly from people they know well, and they rely on
personal familiarity, more than on science or theory, before they decide to test a change”
(p. 1972).
David J. Stanley, John P..Meyer and Laryssa Topolynytsky (2005) speak of the
benefits of employing change agents in their study of employee cynicism and change
resistance. Their findings indicated that while communication is important in overcoming
change resistance, management faces an additional challenge when that resistance is
based on employee cynicism. Employee cynicism is distinguished from other forms of
resistance because it is “based on the disbelief in motives [which] cannot be easily
addressed with facts and figures” (p. 457). To address the distrust in organizational
motives, the researchers suggest management “identify trusted individuals within an
organization, who once convinced of the sincerity of managements’ motives, can help to
gain the support of employees at large” (p. 458).
Nancy Lorenzi and Robert Riley (2000), in their studies of change management in
health care organizations, found that past medical advances were primarily stand-alone
systems, affecting limited and specific areas. However, as time has passed, more and
more advances were affecting more heterogeneous groups and areas. As a result, major
challenges to innovation success are behavioral. “Effective leadership can sharply reduce
the behavioral resistance to change” (p. 116). “Creating change starts with creating a

vision for change and then empowering individuals to act as change agents to attain that
vision” (p. 118).
The communication process between early adopters and the early majority is
referred to by Ikujiro Nonaka, Georg von Krogh and Sven Voelpel (2006) as
organizational knowledge creation. According to Nonaka et al., “organizational
knowledge creation is the process of making available and amplifying knowledge created
by individuals … and connecting it with an organization’s knowledge system” (p. 1179).
In their research they address the concept of knowledge activists. Knowledge creation
theory states that knowledge is “created locally, where tasks are attended to, problems
defined and resolved.”
Therefore a knowledge activist must be able to share that knowledge beyond the
context and into the remaining areas of the organization. They do so by coordinating
knowledge creation, initiatives, and determining opportunities for knowledge sharing. A
knowledge activist will “bring different knowledge sets and introduce ‘creative abrasion’
that leads to conflicting ideas but also new possibilities to create knowledge” (p. 1187).
Many studies tout the benefits of effective communicators. To ensure an
innovation is heard and accepted, the communication method plays a key role. Change
agents control the dissemination of information in such a way as to “provide an overall
direction for the knowledge creation” (Inonaka, et al., 2006, p. 1188). As a result, it is
imperative that organizational leaders take heed to identify the correct change agents for
individual change efforts. Studies have found that “opinion leaders [are] not concentrated
in the upper brackets…but [are] located in almost equal proportions in every social group
and stratum” (Katz, 1957, p. 72). In his analysis of research done on opinion leaders, Katz
(1957) found that there are certain traits that make a person more likely to be an opinion

leader: (1) who the person is (possessing certain value sets), (2) what the person knows,
and (3) who the person knows. “Influence is often successfully transmitted because the
influencee wants to be as much like the influential as possible” (p. 73); however, what an
individual knows and how accessible he or she is will also play an important role.
In order for change agents to be successful, they must be selected carefully.
Electing opinion leaders based solely on their position in an organization is a guarantee
for success.
Opinion leaders and the people whom they influence are very much alike and
typically belong to the same primary groups of family, friends and
coworkers. While the opinion leader may be more interested in the particular
sphere in which he is influential, it is highly unlikely that persons influenced
will be very far behind the leader in their level of interest. Influentials and
influencees may exchange roles in different spheres of influence (Katz,
1957, p. 77).
There must be a level of trust and respect among the communicator and those with
whom he or she is communicating for there to be any influence.
The Innovation-Decision Process
A communication process must undergo a series of steps in order to achieve a
successful change effort. The decision-innovation process “is the process through which
an individual passes…to [reach] implementation and use of [a] new idea” (Rogers, 1995,
p. 20). Knowing the stage of the innovation decision process is essential to the
communication process. This knowledge allows for proper preparation of communication
messages. The process consists of five stages as illustrated in Figure 1.
Figure 1.
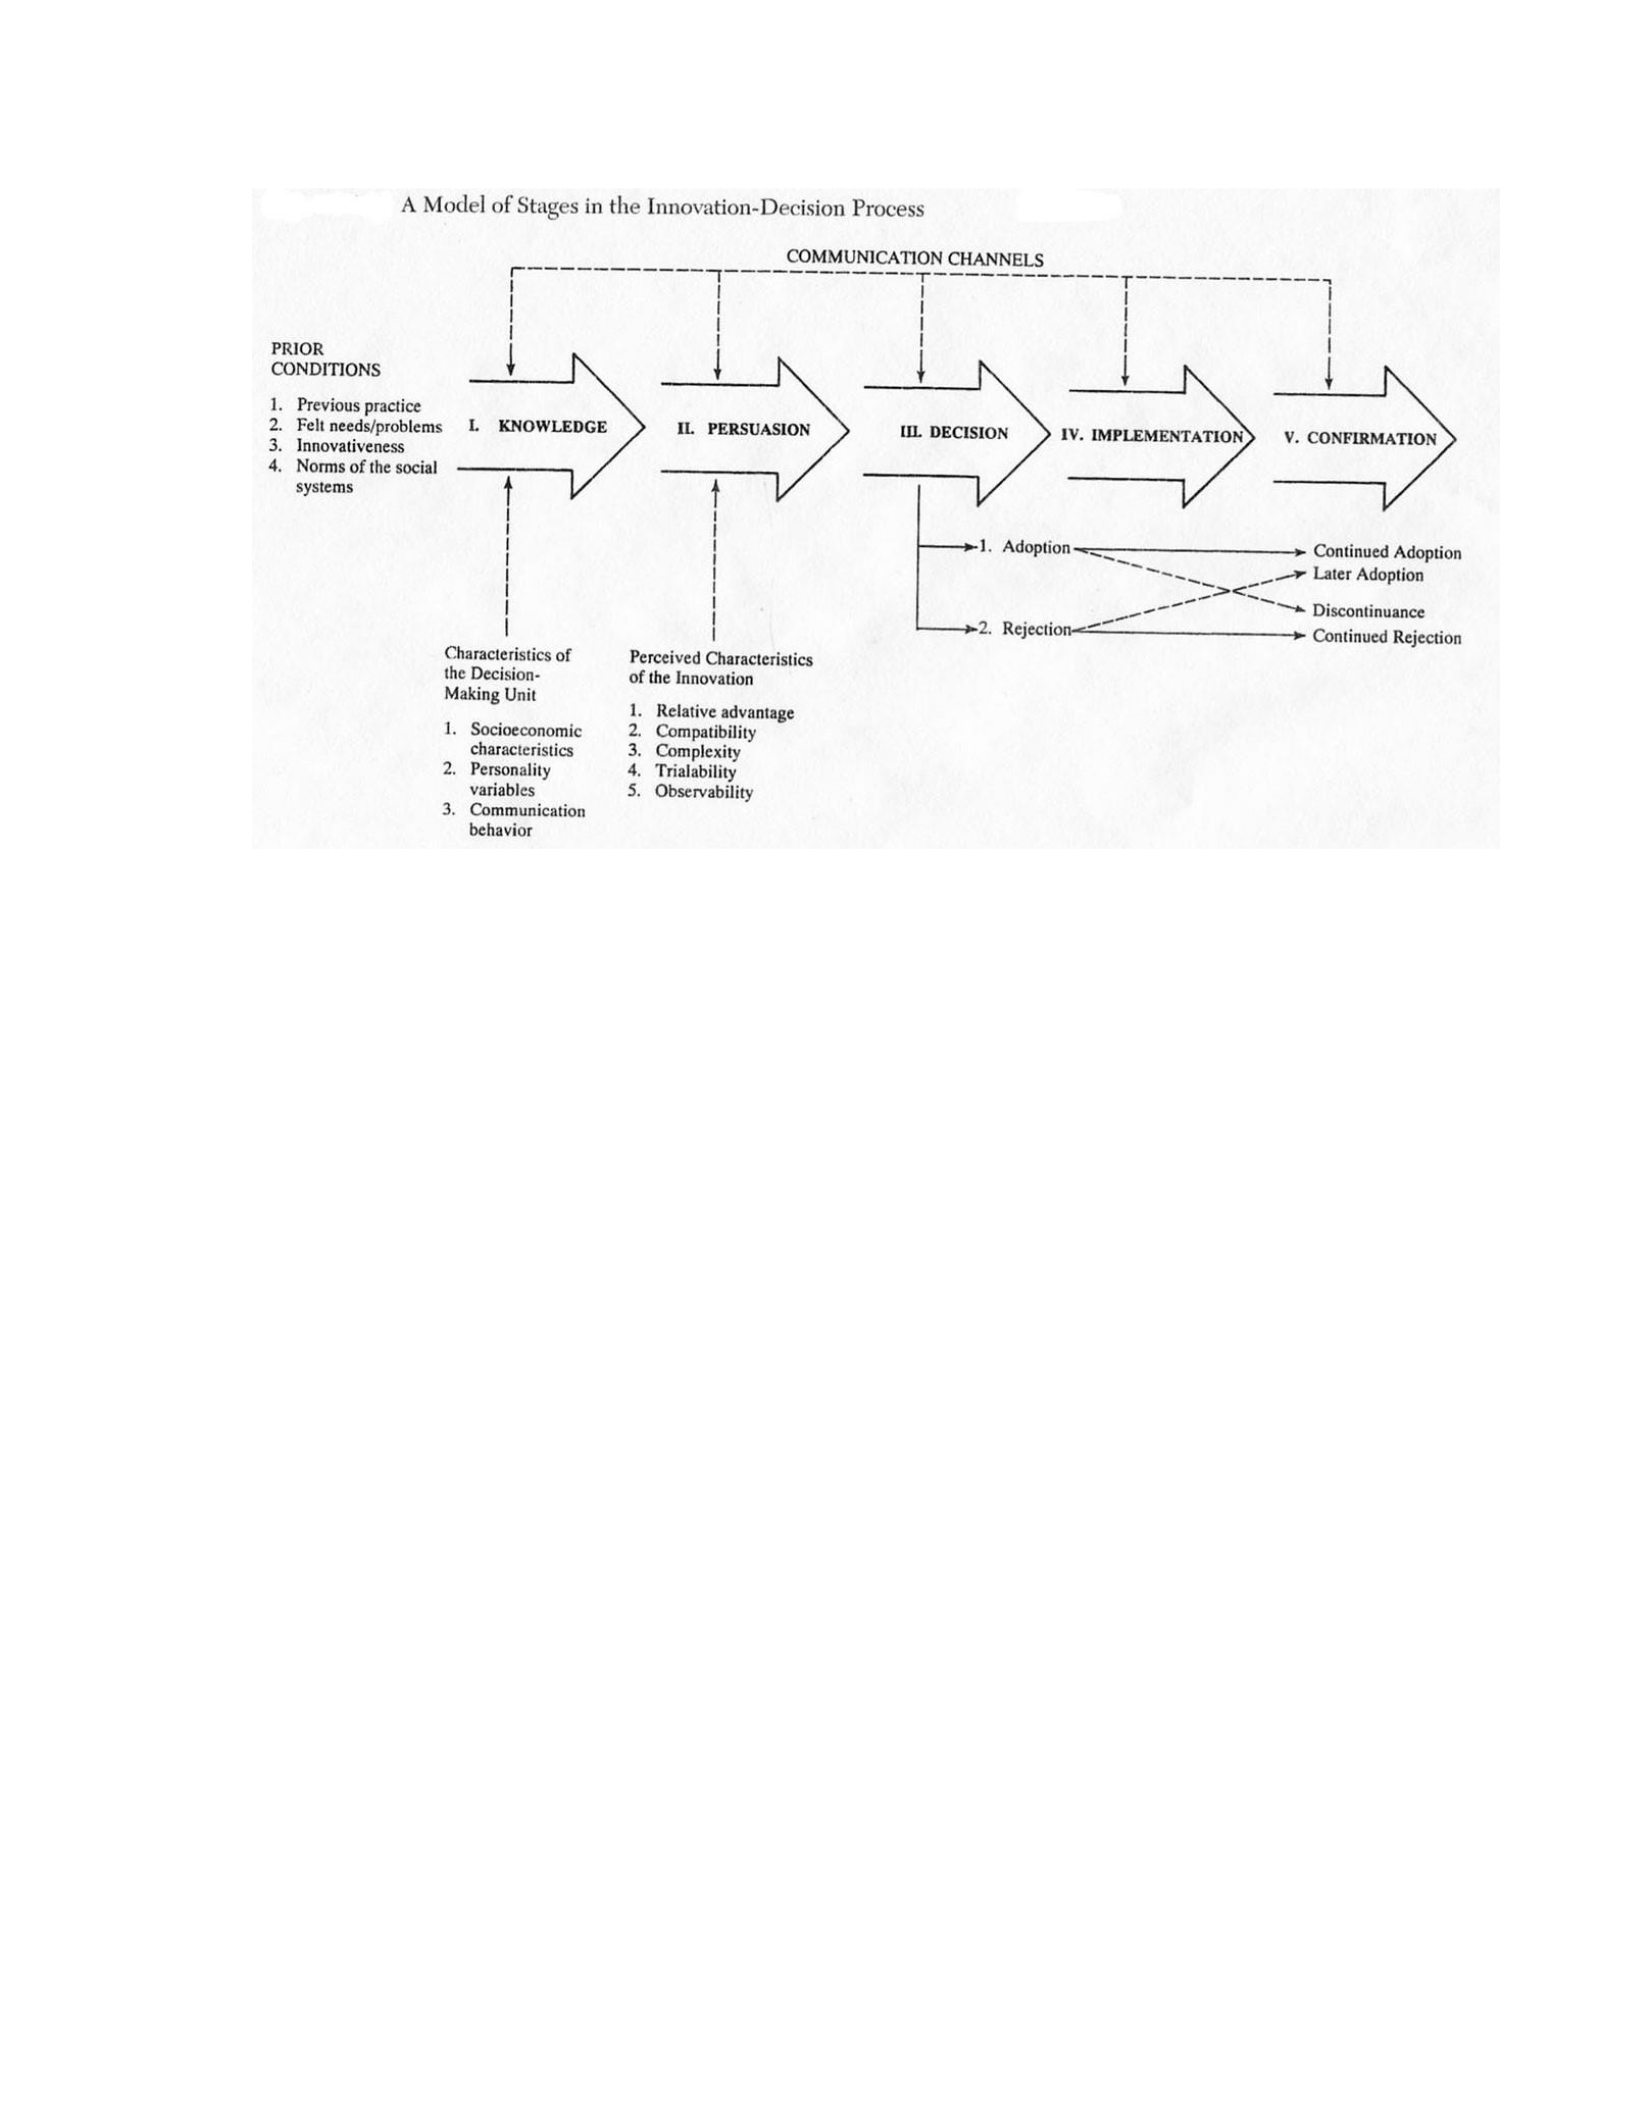
The knowledge stage of the process is when a group or an individual learns about
the innovation. During this stage individuals mainly seek “information that reduces
uncertainty” (Rogers, 1995, p.21). Therefore, the knowledge stage is an
“informationseeking and information-processing activity” (p. 165). Here individuals seek
to learn what the innovation is and in which ways it will affect them. Diffusion of
innovations theory states that during this stage there are three types of knowledge
gathering:
awareness-knowledge, how-to knowledge, and principles-knowledge.
During awareness-knowledge an individual knows that the innovation exists;
how-to knowledge is the information necessary for using the innovation; and
principlesknowledge is “information dealing with the function principles underlying how
the innovation works” (Rogers, 1995, 166).
In the knowledge stage, information exchanged is generally one-way. This is
when communicators educate individuals about an innovation. However, the

communicators must soon prepare for a two-way communication process. Once
individuals are aware of the innovation, it is only a matter of time before they will have
questions. Furthermore, additional research has demonstrated that two-way
communication practices are more favorable than one-way communication. The
persuasion stage of the decision process occurs when individuals form attitudes towards
the innovation. It is during this stage that an individual “becomes more psychologically
involved with the innovation” (Rogers, 1995, p. 168). At this time, providing
“evaluation information,” is most likely to reduce the uncertainty associated with the
“innovation’s expected consequences” (p. 21). Organizations must take heed to provide
individuals with avenues to gather this information and take the initiative to provide
channels for two-way communication. It is during this time that individuals are more
likely to seek information from their peers. If there is no information available to reduce
uncertainty, then individuals will rely on information they receive through the grapevine
and the speculations of their peers. It is wise for organizations to keep up-todate on the
information disseminated through the grapevine as it is an information-rich indication of
individuals’ attitudes towards change (Rogers, 1995).
After the persuasion stage comes the decision stage. During this stage individuals
engage in “activities that lead to a choice to adopt or reject the innovation” (Rogers,
1995, p.21). One of the best ways to cope with the “inherent uncertainty about an
innovation’s consequences is to try out the new idea on a partial basis” (Rogers, p. 171).
Testing out a change program in one department and then spreading it to others can aid its
adoption. A trial by others “provides a kind of vicarious trial for an individual.” (Rogers,
p. 171). It also provides an organization with valuable information. Trial runs will make
difficulties with implementation visible. This can help prepare communicators for

roadblocks in widespread implementation and result in a smoother transition for the
change effort. Once decision makers come to an understanding on the best approach, the
implementation and confirmation stages will begin.
During the implementation phase individuals put the innovation to use and during
the confirmation stage they seek reinforcement on the decision to accept the innovation
(Rogers, 1995). If there is no opportunity for a trial run, then adoption problems become
visible during the implementation stage. Change implementers must then evaluate and
revise message strategies to keep the process moving forward. It is important to note, that
communication is essential throughout the adoption on any innovation, from beginning to
end.
Innovations in Organizations
Diffusion of innovations research initially focused on how individuals adopt or
reject an innovation. Later studies stressed the “implementation stages involved in putting
an innovation to use in an organization” (Roger, 1995, p. 371). The implementation
decision process is much more complex within an organization. It “typically involves a
number of individuals, each of whom plays a different role in the innovation-decision
process. Further, implementation amounts to mutual adaptation in which the innovation
and the organization change in important ways” (p. 372).
For innovations in an organization there appear to be three kinds of innovationdecisions.
1. Optional innovation-decisions – choices to adopt or reject an innovation that are
made by an individual independent of the decisions by other members of a
system.
2. Collective innovation-decisions – choices to adopt or reject an innovation that are
made by consensus among the members of a system.
3. Authority innovation-decisions – choices to adopt or reject an innovation that are
made by a relatively few individuals in a system who posses power, status, or
technical expertise (Rogers, 1995, p. 372).

In addition, innovativeness in organizations is related to individual leader characteristics,
internal organizational structure and external organizational characteristics.
Research has indicated that centralization in organizations is negatively associated
with innovativeness. This means the more power is “concentrated in an organization the
less innovative the organization tends to be” (Rogers, 1995, p. 380). This is because the
leaders are making the change decisions and filtering them down within the organization.
The problem with this is leaders are often poorly equipped to identify problems because
they are not in the midst of everyday organizational activities, or in the trenches. Their
decisions are met with resistance because employees feel that the individuals making those
decisions do not understand what employees’ everyday jobs are really about (Rogers,
1995).
Another organizational characteristic that can affect the adoption of
organizational change is its degree of formalization. Rogers describes this as the ‘degree to
which an organization emphasizes following rules and procedures in the role performance
of its members” (p. 380). This can hinder the consideration of innovations, but may
encourage their implementation. Strictly following rules can affect creativity because
people are often not encouraged to think outside the box. However, if an organization
decides to implement any kind of change effort, employees that are used to adhering to
rules may simply follow suit with organizational decisions (Rogers, 1995).
Organizational interconnectedness can also affect the adoption of an innovation.
Interconnectedness in an organization is the degree to which “units in a social system are
linked by interpersonal networks” (Rogers, 1995, p. 381). This can be very useful in
spreading innovations throughout the organization, but it can also make things very
difficult, it is all contingent upon employee reactions to the change effort.
When it comes to organizational research and innovations, studies have primarily focused
on the implementation rather than the adoption or rejection of innovations. This is because
organizations are often seen as “constraints or resistances to innovations” (Rogers, 1995,
391). On the other hand, the difficulties faced by an organization in implementing a change
effort can also be attributed to an ill fit between the innovation and the organization
(Rogers, 1995).
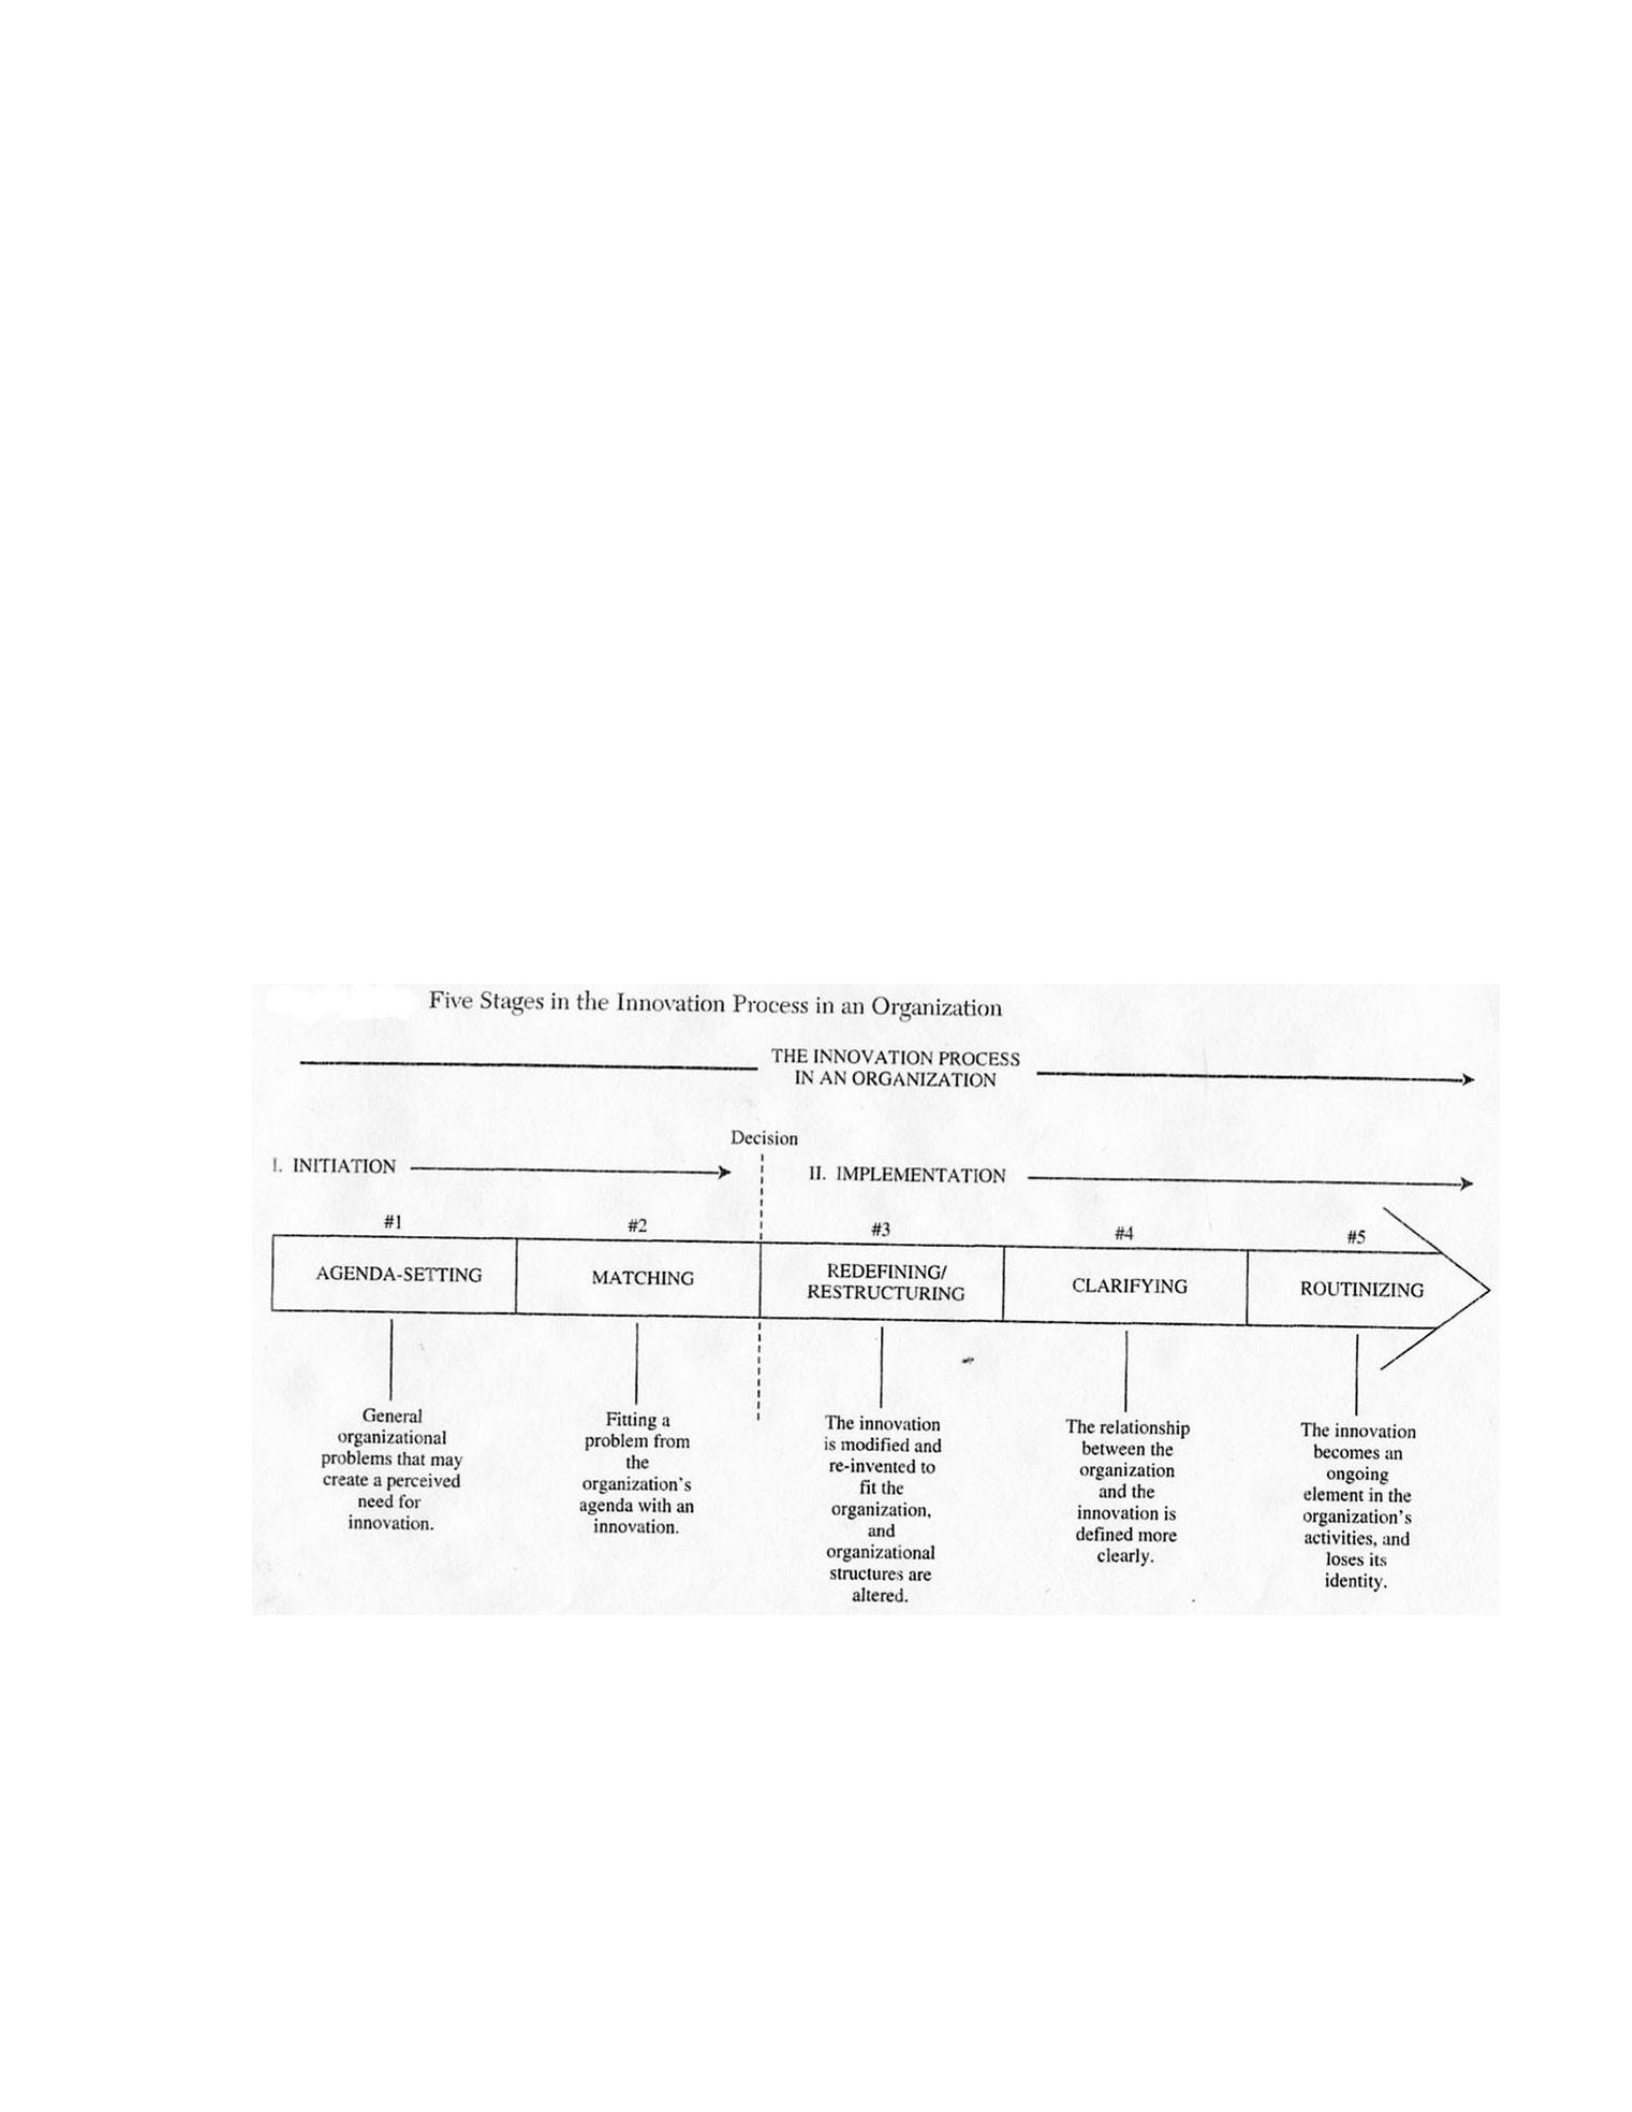
The innovation-decision process for organizations consists of similar steps as that
for individuals. However, it is divided into two parts, as illustrated in Figure 2. The first
phase is the initiation subprocess and the second phase is the implementation subprocess
(Rogers, 1995).
Figure 2
Initiation Phase
The initiation phase occurs when all the information gathering and planning for the
adoption of an innovation takes place and ends once the organization make a decision to
adopt. The initiation stage consists of agenda-setting and matching processes. During

agenda-setting an “organizational problem that may create a perceived need for an
innovation is defined” (Rogers, 1995, p. 391). It is an ongoing process within organizations.
To continue operating efficiently, an organization must understand the steps it must take to
improve. During agenda-setting problems are identified and prioritized; often a time
consuming task (Rogers, 1995).
Once problems are identified and prioritized the matching stage begins. This is
when organizational problems are fit with appropriate innovations or change efforts. It is
when “organizational members attempt to determine the feasibility of the innovation in
solving the organization’s problem…” and it includes “thinking about the anticipated
problems that the innovation might encounter if it were implemented” (Rogers, 1995, p.
394)
Implementation Phase
Once an organization decides to adopt an innovation the implementation
subprocess begins. It consists of three stages: redefining/restructuring, clarifying and
routinizing (Rogers, 1995).
During the first stage, an innovation is worked to fit the organization’s needs and structure
more closely. At the same time, organizational structure is modified to fit the innovation.
To a certain degree, both the innovation and the organization must change. “This mutual
adaptation must occur because the innovation almost never fits perfectly in the organization
in which it is to become embedded” (Rogers, 1995, p. 395).
Next comes the clarifying stage. This occurs when an innovation is put to use in an
organization so that the innovation’s meaning becomes clearer to its members. It consists
of a “social construction.” “When a new idea is first implemented in an organization it has
little meaning to the organization’s members” (Rogers, 1995, p. 399). This results in

uncertainty. The clarifying stage is when questions about the innovation are answered so
that organizational members can gain a common understanding.
Common understanding occurs over time through a social process of human interaction.
Finally, comes the routinizing stage. It is when the innovation has become a regular
part of the everyday activities of organizational members. At this point the innovation
processes is complete.
Change Communication: Two-Way vs. One-Way Communication
So far, the theories discussed have illustrated the need for effective and
appropriate communication to implement successful change programs. Additionally,
several research studies have demonstrated the importance of continued communication
during change efforts.
In one such study, Goodman and Truss, 2004, analyzed two organizations’
communication strategies when implementing their change programs and the effects the
strategies had on the employees. In particular, the study focused on the timing of the
change messages, the use of appropriate media, and their effect on employee uncertainty.
For each organization the researchers used the following approaches:
A review of company documentation; unstructured interviews or
electronic communication with a small number of staff to ascertain the
principal issues in the change program and to provide essential background
information; three semi-structured interviews in each organization with
senior managers to explore the design and purpose of the communication
strategy; and a questionnaire of a random selection of two-thirds of
employees in each organization, excluding senior management, to uncover
reactions to the change and communication strategies (p. 221).
The semi-structured interviews yielded important information. One of the
organizations primarily used one-way communication, while the other company used a
combination of one- and two-way communication. These communication efforts

consisted of face-to-face communication, and a reward system to celebrate individuals’
successes during the change program. Results from employee surveys demonstrated that
employees in both organizations preferred face-to-face, two-way communication about
change programs and that they would like their opinions to be included in the decision
making process (Goodman & Truss, 2004).
Overall, the research results were quite interesting. The study found that both
organizations were unsuccessful in the implementation of their change processes even
though one of the organizations used two-way communication. Findings indicated that
the organization still neglected some key elements in its communication strategy. Their
research indicated that management was “out of touch with employee concerns…and
they did not understand how the changes would affect them” (Goodman &Truss, 2004,
p.225), which indicates the importance of keeping employees in mind when developing
any communication strategy. According to the findings, communication should be
twoway, and employees should be given the opportunity to provide feedback. Also, as a
part of any communication strategy, organizational leaders should continuously evaluate
the results to ensure that strategies continue to be effective by revising approaches that
are not providing results.
Employee Involvement in Change Efforts
These research findings go hand in hand with the findings of Prashant Bordia,
Elizabeth Hobman, Elizabeth Jones, Cindy Gallois and Victor Callahan, 2004. Bordia et
al., studied uncertainty in organizations during times of change. They hypothesized that
“management communication and participation in decision-making would reduce
uncertainty and increase feelings of control” (Bordia et al., 2004, p.507). Uncertainty,
defined as “an individual’s inability to predict something accurately” is the source of

stress that often causes resistance to change in organizations (p. 508).The study focused
on individuals’ level of uncertainty during change and the ways in which this uncertainty
can be reduced.
As cited earlier, effective management communication is one way to reduce
uncertainty. However, Bordia’s et al., study (2004) went a step further. This study also
proposed that participation in decision-making would positively aid the management
communication process in effectively implementing organizational change. Literature on
this topic typically indicates that participation in decision making has a positive impact.
“It has been shown that when employees are involved in the implementation of new
programs they are more likely to perceive the program as being beneficial. Employee
involvement in tactical decisions has been found to lead to employee acceptance or
openness toward change” (Bordia et al., 2004, p.515).
The findings of the study support the findings of Goodman and Truss.
“Management communication is effective in reducing uncertainty about strategic aspects
of change,” but to “reduce feeling of uncertainty…participative strategies are required”
(Bordia et al., 526). The study also found that “by being involved in and contributing to
decision-making, employees experience less uncertainty about issues affecting them and
feel more in control of the change outcomes” (p. 526).
Information Access and Its Effects
Tourish, Paulsen, Hobman and Bordia (2004), also studied the effects of
organizational change on levels of trust and uncertainty in employees. Their findings
were similar to those discussed previously, with one notable exception. This study
provided a unique opportunity to observe and study those affected negatively by the
change efforts as well as those affected positively. This research focused on a downsizing

change effort in a hospital. Subjects affected negatively were those employees who were
let go, while those affected positively were those who did not lose their jobs. This study
demonstrated that individuals undergoing change efforts are all affected similarly
regardless of which end of the spectrum they fall into. Tourish et al. (2004) found that the
communication efforts espoused by the organization were largely to blame for the anxiety
levels held by both groups of employees. By holding back information, senior managers
left middle and lower level managers with little or no information to pass on to employee
concerns. As a result, middle and lower level managers could not elaborate or appease
employees. They received the same amount of information as employees did and were at
a loss when it came to answering questions. Therefore, employees were left to speculate
and rely on rumors to gather information.
The results of this study provide further evidence of the importance of effective
communication efforts. Organizational change often rouses feeling of fear that lead to
resistance. Effective communication can lower these constraints and the tendency to rely
on rumors as sources of information. Most importantly, it emphasizes the effects of
change. Both those who are affected by changes and those who are not will suffer the
same amount of distrust and uncertainty when provided with insufficient information.
Another important finding to take notice of is that research participants indicated that
information alone would not have been enough to lower their uncertainty levels, further
emphasizing the importance of two-way communication. Employees felt it was necessary
to be able to ask questions and have the opportunity to engage in discussions regarding
what is to be expected during a change effort (Tourish et al., 2004).
Internal Communication and Employee Motivation:

The necessity of communication is obvious from the findings of the previous
studies. However, studies have only discussed the need for communication strategies, not
the reason internal communication is successful in aiding change efforts.
“As the trend toward organizational change continues, strong internal
communication programs will increase in importance. Bridging the gap
between employees and managers has become a critical goal for
organizations today. Massive organizational changes…have turned
traditional employee confidence and loyalty to uncertainty, antagonism and
fear about the future” (Heidelberg, 1999, p.5)
Heidelberg (1999) proposes that internal communication is not only necessary
during times of change, but it has a greater purpose than that of persuasion. Internal
communication serves as a tool for understanding and fostering employee motivation.
Due to the psychological side effects of change, it has been noted that employees undergo
an emotional process that in turn leads to change resistance in order to fight the anxieties
that change brings. When internal communication is seen as more than just a one-way
attempt at persuasion it opens up an avenue for employee motivation. In order to maintain
employees motivated they must have a sense of job satisfaction.
Therefore, internal communication can serve for more than just change
implementation. It can help shape and establish an organizational culture that fosters high
levels of employee morale and therefore high levels of employee motivation.
Given the scope and nature of the change taking place at the medical facility and
the findings from previous studies on communication and change management, it would
seem obvious to assume that the organization’s training program would be beneficial to
the implementation of their change effort. This study sought to determine if the training
program is not just beneficial, but also effective in facilitating the adoption of the new
electronic medical records technology among its most discerning and resistant members.

The audience for this training program posed a more difficult hurdle because doctors at
the medical facility are not employees, but shareholders and board members who could
ultimately decide to take their practice elsewhere. For them, it is not just a matter of
adopting a change their employer is enforcing, loss of status or uncertainty in their
position, but instead it is a matter of how this change will ultimately be of benefit to the
everyday operations of their medical practice. If they are to change their set ways, they
must understand the beneficial implications of the new software.
The medical facility’s decision to implement this innovation was an authority
innovation decision (a top down decision). A select group of individuals, possessing the
power and expertise, chose the innovation and then filtered the decision to the rest of the
members of the organization (Rogers, 1995).
As a result, this research study set out to determine the effectiveness of the
training program in:
• Increasing user knowledge of the new computer program
• Increasing user understanding of the benefits of the new computer program
• Reducing user resistance and feelings of uncertainty towards the new
computer program
• Increasing user acceptance and adoption of the innovation
Research Hypotheses:
H1: Communication training reduced participant anxiety about the change.
H2: Communication training increased user understanding of the need for the innovation.
H3: Communication training improved levels of confidence using the innovation.
Research Questions:

R1: How did the training communication affect participant groups (occupation, gender,
age)?
R2: Did participants in the training believe the training functionally reduced anxiety and
improved acceptance of the change?
R3: How did participants perceive the changes?
R4: Were the changes viewed as organizational improvements?
CHAPTER 3:
Methodology
This research employed a multiple methods approach to obtain information in this
study. Both survey and qualitative data helped find trends that determined the rise or fall
of anxiety and uncertainty levels (quantitative) and allow for a more detailed
understanding of the ‘why’ behind any group changes discovered (qualitative).
Doctors were divided into beginner and advanced user groups. Advanced users
had some working knowledge of the current computer system from already having many
of their patient files on the current server, and were able to navigate through it with ease
(J. Delatorre, 03/30/06). The rest of the physicians fell into the beginner category. The
advanced users were trained and expected to use the new system by the October 24
launch date. Physicians categorized as beginners were trained with their departments for
the later launch dates. The first group of beginner physicians began their training in
November and were expected to be ready to change over by December 11, with
subsequent groups training and going live over the span of six months. Because
physicians are so busy, they posed a special challenge. They had to learn the new system,

but do so while still handling their regular patient load. To accommodate this, there were
nine, four-hour computer-based training sessions offered on Saturdays through the
beginning of April (see Appendix D). During the span of these four hours, the physicians
were taught the how-to’s of the new system, and were given the opportunity to return to
any other training session if they felt they need extra help in any specific section.
In doing so, the training would “get the advanced users to fully understand and be
comfortable with the new software, and get the basic users [to] an intermediate level of
familiarity with the program” (J. Delatorre, Interview 03/30/06). Ideally, doctors would
become acclimated with the program and feel comfortable with using it on a daily basis,
understand the benefits it would bring and demonstrate less resistance to using the new
technology.
The medical facility understood that users at the beginner level were unlikely to
reach an advanced user stage after the training program; however the intention was to
make them feel comfortable using the new system, so they would be more inclined to
accept it and continue making strides in learning the program with daily use.
Quantitative Methodology
Data for this study was collected using two questionnaires (in a pre- and post training
setting) surveying employee groups participating in the training program. The first
questionnaire (see Appendix A) was used to assess their attitudes towards the new
practice management system prior to the training program, and the second (see Appendix
B) to assess their attitudes regarding the practice management system after the training
program to determine if there is any change. Secondary research has indicated that
organizational change management is dependent on communication to reduce anxieties
and feelings of uncertainty that often result in resistance to an organizational innovation.

A total of 90 members of the medical staff (physicians, physician assistants and nurse
practitioners) were required to undergo training. However, because the full conversion
into a paperless facility was spread over six months, not all departments were trained at
the same time. Each group has approximately five to ten individuals. This research
focused on the first employee groups undergoing training that were classified as
beginners. Because of the size of the group participating in the training program, all
trainees were asked to participate, making the survey sample a purposive sample.
Surveying several training groups would allow the researcher to gather information from
a representative sample.
Survey methodology was used to gather as much information from the group as
possible within a relatively short timeframe. This research study used surveys to gather
information on any behavioral changes in attitude (anxiety and uncertainty levels)
regarding the innovation and change effort, resulting from the training program.
Seven-step, Likert-scaled questions were employed to determine any change in
attitude toward the innovation that helped facilitate its adoption and to gauge whether
participants felt theoretical components of the Diffusion of Innovations Theory were
present in the implementation of the innovation.
Qualitative Methodology
Qualitative data collection, in the form of open-ended questions, was added to the
questionnaires (see Appendix A and B) to give the research a level of depth and detail that
would otherwise be absent from the survey instrument. Quantitative data would allow the
researcher to determine if there is any change in behavioral attitude toward the innovation
as a result of the communication effort, but would not provide any details regarding the
reasons for any change in behavior, or the reasons for the feelings of anxiety and

uncertainty (if any are found). Qualitative questions would give the researcher more
details regarding the whys behind the behavioral changes that may occur.
Qualitative data collection would make it possible to answer the proposed research
questions. Adding the open-ended questions to the end of the survey instrument provided
a way to gather detailed information from this group of individuals about how they felt
about both the changes and the need for the change. As mentioned earlier, the medical
staff was a busy group, and they were already setting aside time to attend the training
sessions. In-depth interviews and focus groups would require more imposition on their
already taxed schedules and it was determined they would not be as effective. It was
decided that having a representative and captive sample of employee groups present at the
training sessions was the ideal time to gather the necessary information. Keeping the
qualitative portion of the research as part of the survey instrument would make the
process easiest for participants, while still providing a well-rounded understanding of the
concerns and attitudes participants hold toward the change program.
Although 90 individuals will undergo training, this study involved a representative
group, although small. The results of this the study are treated as a case study from which
others can examine the pros and cons of the approach taken by the Florida medical
facility to implement an innovation. It serves as a reference to some of the obstacles
organizations may face during times of change.
CHAPTER 4

Results
This section reviews the results of various statistical analyses to determine the
influence of training on the use of new technology on group participants. Specifically,
participants in the medical field were trained in the use of a new computer system.
As discussed in the methodology, the researcher administered a survey before and
after each training session. Participant responses were analyzed to determine if there were
changes in reported anxiety, confidence and understanding toward the need for the
innovation. Analysis included Chi-Square, analysis of variance (ANOVA), and paired
ttests. The researcher also examined responses according to participant age group,
occupation and gender.
Breakdown of Training Participants
Survey questionnaires were made up of Likert-scale questions and open-ended
questions to gather as much information as possible on participant attitudes toward the
new practice management system.
Thirty participants took part in the training classes in which the researcher
administered the survey questionnaire. The original training schedule called for only
medical staff to participate in the training. However, due to scheduling difficulties, staff
members in the medical offices (e.g., office managers and medical assistants) were
included in the training communication program with their respective group of doctors
(doctors and their staff members would participate in the training program together).
Of the 30 participants, 60 percent (N=18) identified themselves as part of the
medical staff (physicians or nurses) and 40 percent as “other” (N=12). Thirty-seven
percent were under 41 years of age and 60 percent were over 40. Forty-seven percent of
participants were male (N=14) and 53 percent (N=16) were female. Only 29 respondents

(97 percent) provided information on their age, while all 30 provided information on their
occupation.
Survey Questions
In order to determine participant anxiety, confidence, and understanding of the
need for change, respondents were asked to rate their level of agreement, on a scale of
one to seven (with one meaning “strongly disagree” and seven meaning “strongly
agree”), with various statements in the survey instrument. Pre- and post-training
questions aligning to anxiety addressed participant comfort with the upcoming change,
their view on the amount of time given to prepare and plan for the change, the practice
management system’s user-friendliness as well as the training program’s usefulness.
Those related to understanding the need for the change addressed the innovation’s
potential benefits, as well as asked if participants understood the reason for the change.
Finally, statements aligning to confidence were related to participant’s view of the
practice management system’s usability, their expectations of the training program (if
they expect it will be difficult, then likely not confident in their ability to learn/use
innovation) and whether those expectations were met.
Means for individual survey instrument questions are found in Appendix D and E,
grouped according age, gender, and occupation. The means for individual questions were
aggregated to create one variable for anxiety, confidence, and understanding pre- and
post-training.
Quantitative Results
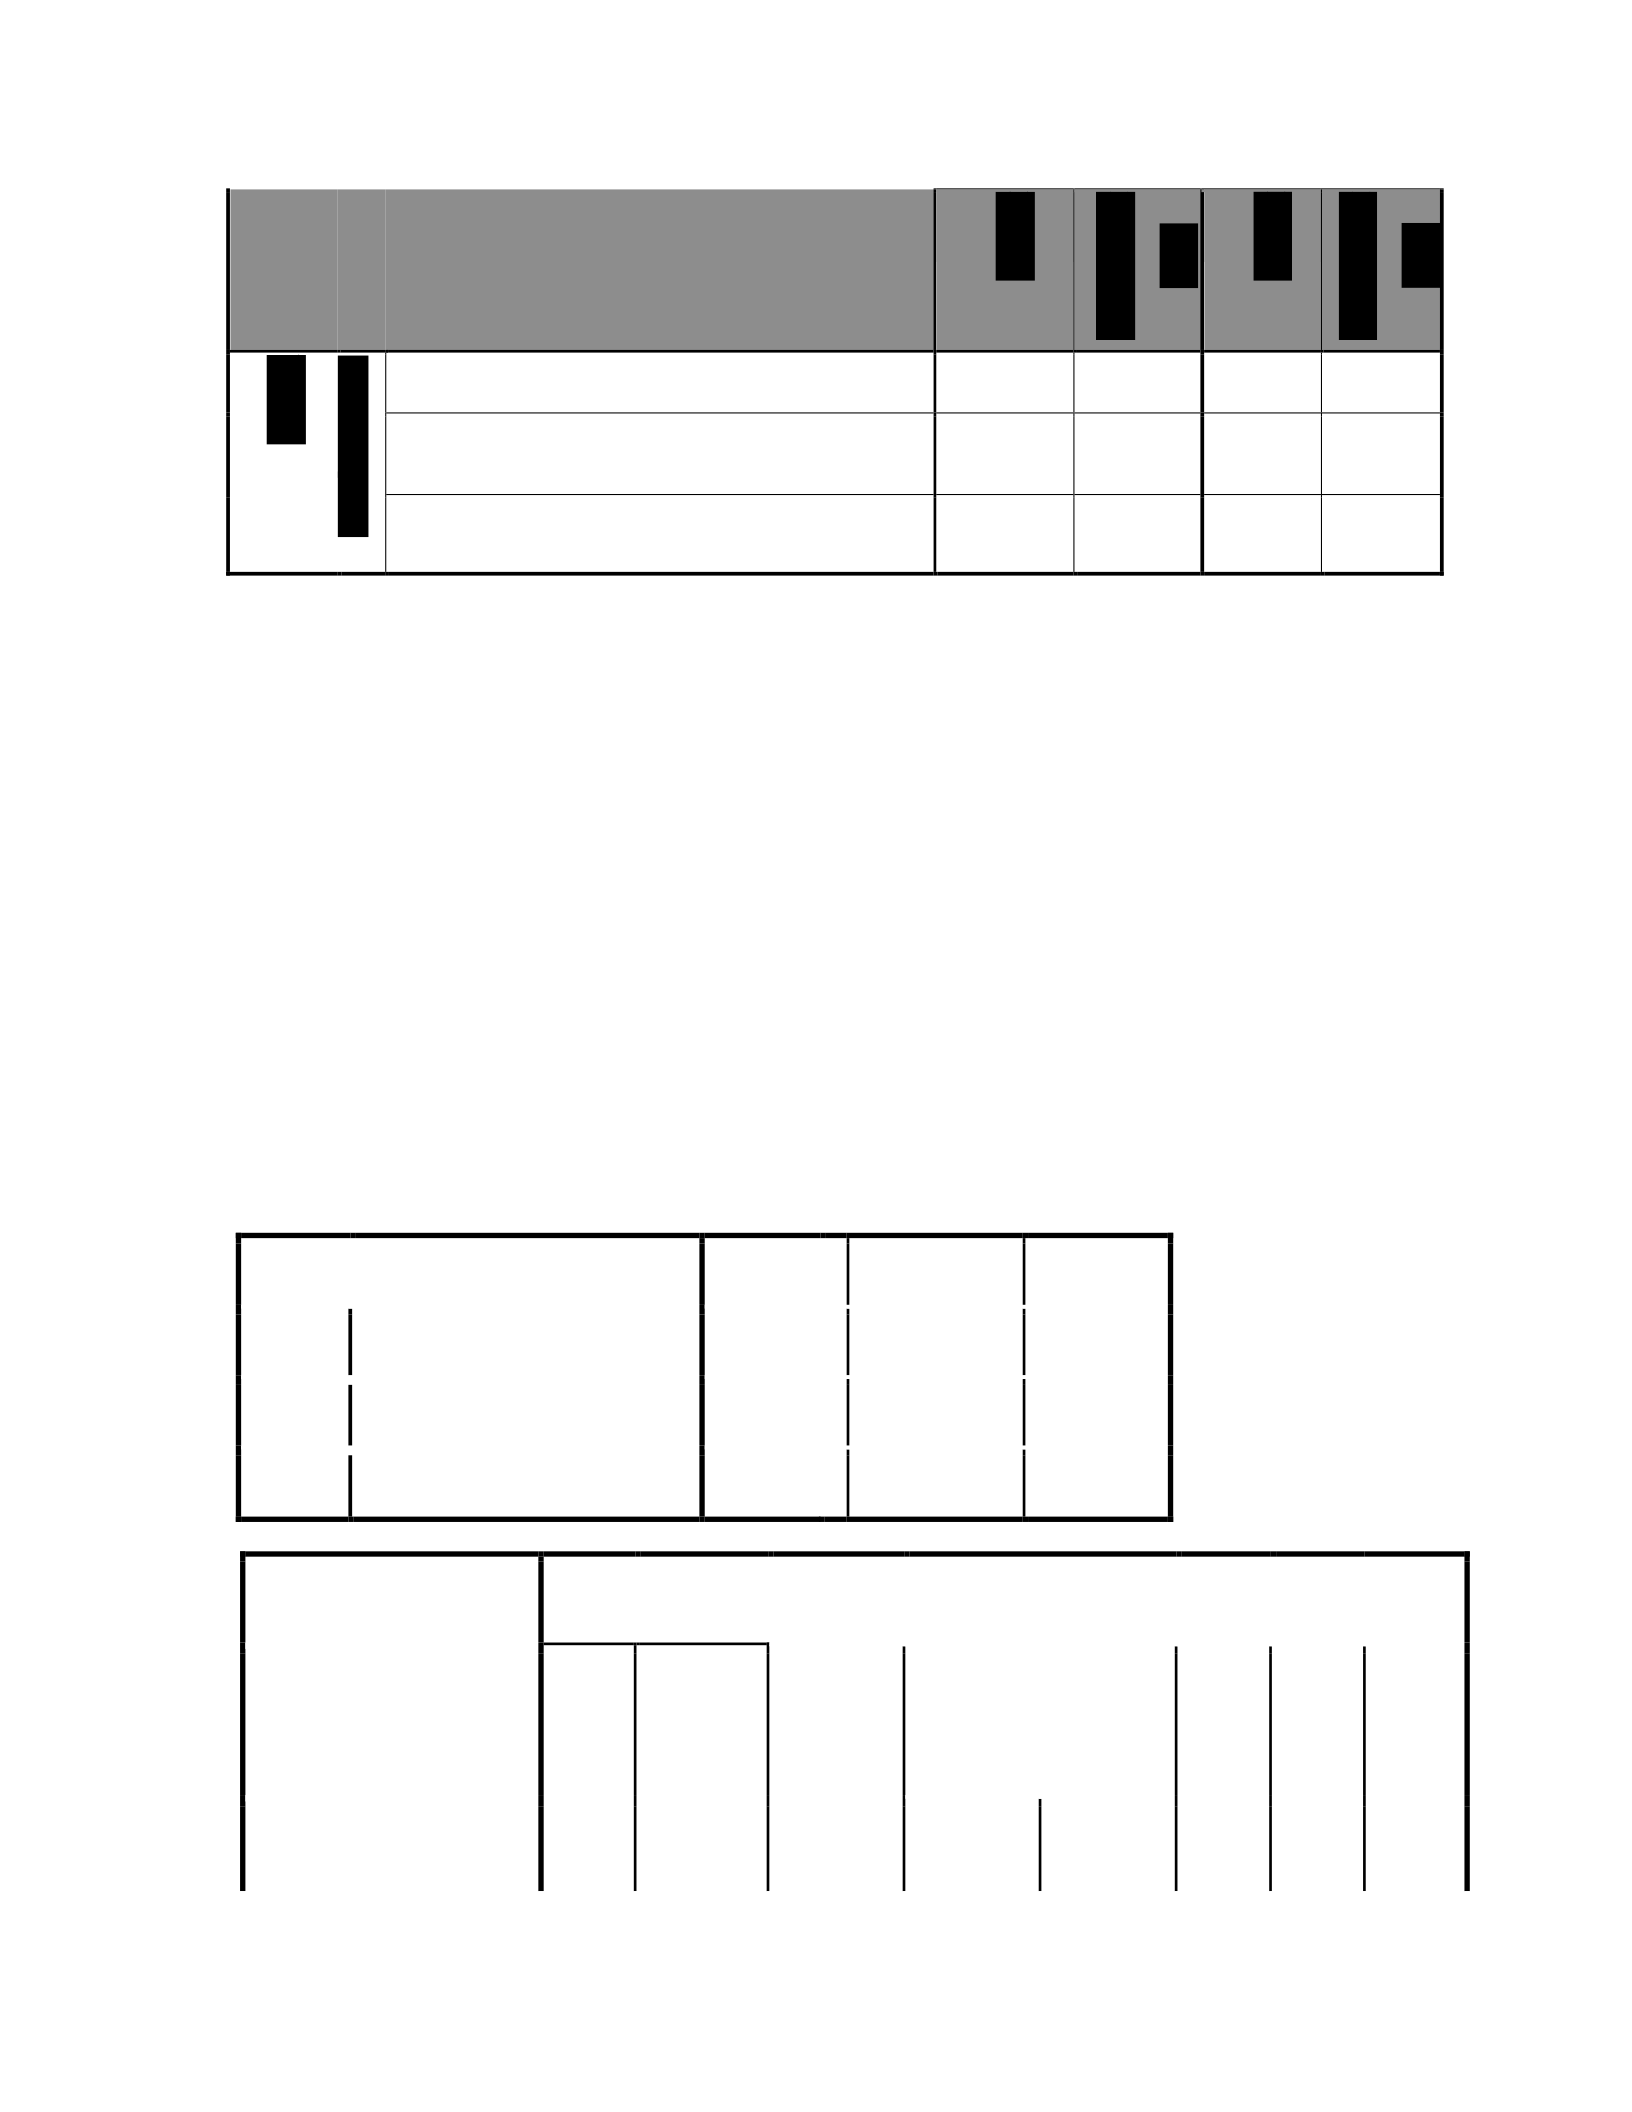
Table 1: Summed Means Pre- and Post-training
Pre-training
Post-training
Anxiety Levels
4.95
1.247
5.30
1.100
Confidence Using the Innovation
5.03
1.235
5.29
1.117
Understanding Need for Change
4.83
1.623
4.69
1.595
Table 1 shows the summed means of questions related to anxiety, confidence, and
understanding the need for change before and after training. Participants reported
increased means for anxiety (+ 0.35) and confidence (+ 0.26), indicating that after
training participants felt more comfortable and less anxious about the upcoming change
and more confident about their ability to use the practice management system. However,
participants reported decreased means for understanding (- 0.14) the need for the change,
which indicates that the training program did not appear to increase their understanding
of the innovation’s relative advantage or explain why they needed to make this change.
Table 2-A: Paired Samples Correlations
N
Correlation
Sig.
Pair 1
Anxiety Pre- & Post-training
30
.663
.000
Pair 2
Understanding Pre- & Post-training
30
.739
.000
Pair 3
Confidence Pre & Post-training
30
.685
.000
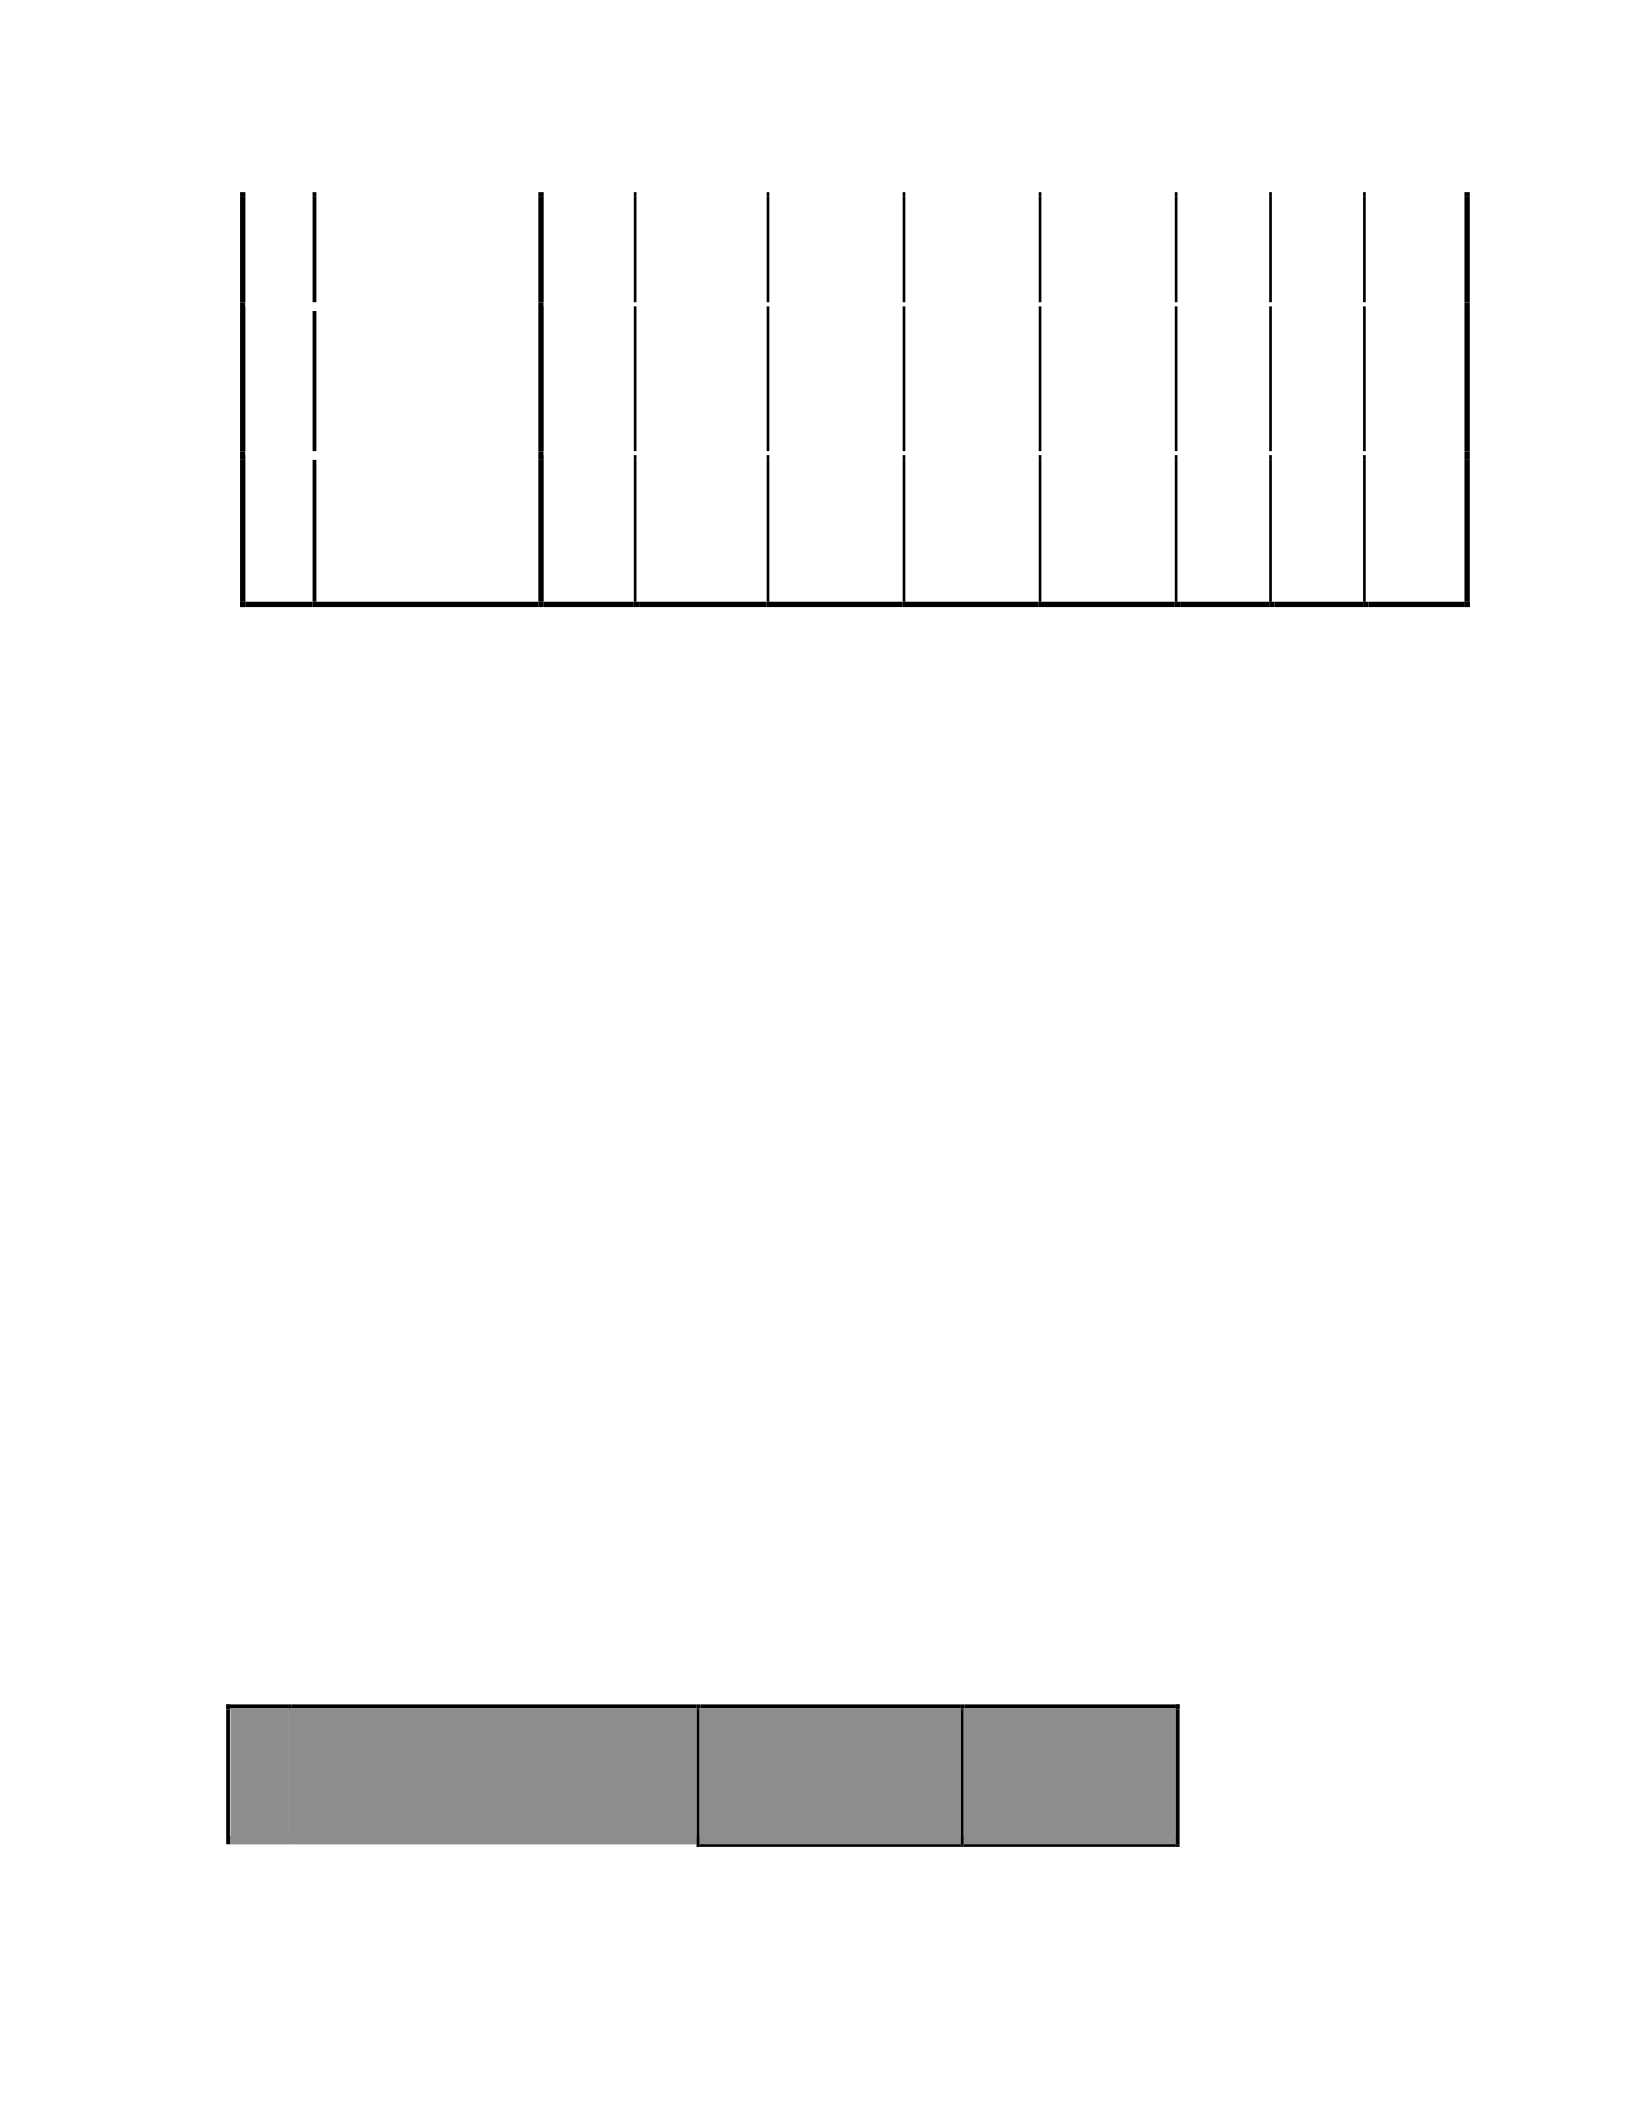
Table 2-B: Paired Samples Test
Paired Differences
Mean
Std.
Deviation
Std. Error
Mean
95% Confidence Interval
of the Difference
t
df
Sig.
(2tailed)
Lower
Upper
Pair 1
Anxiety Pre – Anxiety
Post
-.34762
.97230
.17752
-.71068
.01544
-1.958
29
.060
Pair 2
Understanding Pre –
Understanding Post
.14444
1.16383
.21249
-.29014
.57903
.680
29
.502
Pair 3
Confidence Pre –
Confidence Post
-.26121
.94003
.17163
-.61223
.08980
-1.522
29
.139
T-tests were run on the summed means from Table 1 to determine if the changes
in mean were significant. Tables 2A-B show the results of the paired samples t-tests. The
decrease in anxiety reported after training, although not significant, is approaching
significance (p=0.06). While p>0.05, and not within the 95 percent confidence level, it is
relatively close, and could have been affected by the small size of the sample population.
The increased mean related to confidence was not significant (p=0.139), as shown in
Table 2-B. This suggests that while we saw a positive change in participant confidence
levels, that change was not significantly different from the mean reported pre-training.
The same can be said for means related to understanding the need for change (p=0.502).
To get a better understanding of the training program’s effect on participants, the
researcher also examined participant responses to questions related to anxiety,
confidence, and understanding the need for the change according to participant age,
occupation, and gender. Table 3 shows summed means for age groups, and Table 4 and 5
the results of ANOVA tests and crosstabs, respectively, used to determine significance.
Age Groups
Table 3: Summed Means by Age Group
0-40
(N=11)
Over 40
(N=18)
Anxiety Levels
5.73
1.011
4.47
1.189
Confidence Using the Innovation
5.87
.796
4.50
1.212
Understanding Need for Change
5.60
1.262
4.33
1.701
Anxiety Levels
5.75
.745
4.98
1.213
Confidence Using the Innovation
5.85
.714
4.90
1.199
Understanding Need for Change
5.62
1.245
4.19
1.585
According to Table 3, prior to undergoing training younger participants (ages 40
and under) felt less anxious (m=5.73), more confident (m=5.87), and understood the need
for change (m=5.60) better than participants over 40. Participants over age 40 reported an
anxiety mean of 4.47, a confidence mean of 4.50 and a mean of 4.33 for their
understanding of the need for the change. While younger participants still reported higher
means than older participants after undergoing training, their means remained relatively
the same, with changes of only 0.02 in either direction. On the other hand, older
participants, reported lowered anxiety with a mean increase of 0.51, and increased
confidence with a mean increase of 0.40. However, while younger participants appeared
to remain the same in their reported understanding, older participants reported a decrease
in their understanding of the need for the change by 0.14.
Table 4: One-way ANOVA
Sum of Squares
df
Mean Square
F
Sig.
Anxiety
Between Groups
10.823
1
10.823
8.530
.007
Pre
Within Groups
Total
34.256
27
28
1.269
45.078
Anxiety
Post
Between Groups
4.039
1
4.039
3.567
.070
Within Groups
30.571
27
1.132
Total
34.609
28
Understanding
Pre
Between Groups
10.954
1
10.954
4.542
.042
Within Groups
65.120
27
2.412
Total
76.074
28
Understanding
Post
Between Groups
14.080
1
14.080
6.529
.017
Within Groups
Total
58.221
27
28
2.156
72.301
Confidence
Pre
Between Groups
12.866
1
12.866
11.091
.003
Within Groups
31.322
44.188
27
1.160
Total
28
Confidence
Post
Between Groups
6.126
1
6.126
5.600
.025
Within Groups
29.533
27
1.094
Total
35.659
28
Table 5: Chi-Square Tests Anxiety (pre) by Age
Value
df
Asymp. Sig.
(2-sided)
Pearson Chi-Square
19.797a
19
.407
Likelihood Ratio
26.359
19
.120
Linear-by-Linear Association
6.722
1
.010
N of Valid Cases
29
a. 40 cells (100.0%) have expected count less than 5. The minimum expected count is .38.
Table 6: Chi-Square Tests Anxiety (post) by Age
Value
df
Asymp. Sig.
(2sided)
Pearson Chi-Square
13.072a
15
.597
Likelihood Ratio
17.362
15
.298
Linear-by-Linear Association
3.268
1
.071
N of Valid Cases
29
a. 32 cells (100.0%) have expected count less than 5. The minimum expected count is .38.
Table 7: Chi-Square Tests Understanding (pre) by Age
Value
df
Asymp. Sig.
(2sided)
Pearson Chi-Square
20.505a
20
.427
Likelihood Ratio
27.406
20
.124
Linear-by-Linear Association
4.032
1
.045
N of Valid Cases
29
a. 42 cells (100.0%) have expected count less than 5. The minimum expected count is .38.
Table 8: Chi-Square Tests Understanding (post) by Age
Value
df
Asymp. Sig. (2sided)
Pearson Chi-Square
22.629a
18
.205
Likelihood Ratio
30.178
18
.036
Linear-by-Linear Association
5.453
1
.020
N of Valid Cases
29
a. 38 cells (100.0%) have expected count less than 5. The minimum expected count is .38.
Table 9: Chi-Square Tests Confidence (pre) by Age
Value
df
Asymp. Sig. (2sided)
Pearson Chi-Square
22.629a
16
.124
Likelihood Ratio
30.178
16
.017
Linear-by-Linear Association
8.153
1
.004
N of Valid Cases
29
a. 34 cells (100.0%) have expected count less than 5. The minimum expected count is .38.
Table 10: Chi-Square Tests Confidence (post) by Age
Value
df
Asymp. Sig.
(2sided)
Pearson Chi-Square
19.231a
19
.442
Likelihood Ratio
25.174
19
.155
Linear-by-Linear Association
4.810
1
.028
N of Valid Cases
29
a. 40 cells (100.0%) have expected count less than 5. The minimum expected count is .38.
One-way ANOVA test results (Table 4) indicate pre-training means for anxiety
between the two age groups are significantly different (p=0.007), but the Pearson’s
ChiSquare test (Table 5) indicates that this difference may have occurred by chance
(p=0.41). Post-training, the ANOVA test (Table 4) indicates that there is no longer a
significant difference between participant anxiety according to age group (p=0.07) and
the Pearson’s Chi-Square (Table 6) again indicated this change could have occurred by
chance (p=0.60). Tables 7 and 8 show that means for understanding the need for the
innovation were significantly different between the age groups both before (p=0.04) and
after (p=0.02) training, as were means for confidence (pre-training p=0.003; post-training
p=0.03). Tables 8-10 show that the relationship between age groups and understanding
and confidence could have happened by chance (p>0.05).
Occupation
The following tables show the summed means for reported anxiety, confidence,
and understanding the need for change according to participant occupation (Table 11) as
well as the ANOVA and Pearson’s Chi-Square tests to determine significance (Tables 12-
18).
Table 11: Summed Means by Occupation
Medical Staff
(N=18)
Other (N=12)
Anxiety Levels
4.52
1.204
5.61
1.039
Confidence Using the Innovation
4.50
1.179
5.82
.859
Understanding Need for Change
4.04
1.598
6.02
.674
Anxiety Levels
5.27
1.277
5.35
.818
Confidence Using the Innovation
5.17
1.307
5.44
.780
Understanding Need for Change
4.16
1.76149
5.49
.869
Table 11 shows that prior to training, the medical staff was more anxious
(m=4.52), less confident (m=4.50) and had a lower understanding of the need for change
(m=4.04) than other participants. Others reported means of 5.61 for anxiety, 5.82 for

confidence and 6.02 for their understanding of the need for change. After training, the
medical staff reported decreased anxiety (m=5.27), increased confidence (m=5.17) and a
slightly better understanding for the change (m=4.16). Others indicated slightly higher
anxiety (m=5.35), lower confidence (m=5.44), and decreased understanding of the need for
change (m=5.49).
Table 12: One way ANOVA by Occupation
Sum of Squares
df
Mean Square
F
Sig.
Anxiety Pre
Between Groups
8.574
1
8.574
6.570
.016
Within Groups
36.541
28
1.305
Total
45.116
29
Anxiety Post
Between Groups
.041
1
.041
.033
.858
Within Groups
35.075
28
1.253
Total
35.116
29
Understanding
Pre
Between Groups
28.006
1
28.006
16.201
.000
Within Groups
48.401
28
1.729
Total
76.407
29
Understanding
Post
Between Groups
12.711
1
12.711
5.830
.023
Within Groups
61.052
28
2.180
Total
73.763
29
Confidence
Pre
Between Groups
12.482
1
12.482
11.012
.003
Within Groups
31.737
28
1.133
Total
44.219
29
Confidence
Post
Between Groups
.459
1
.459
.360
.553
Within Groups
35.724
28
1.276
Total
36.183
29
Table 13: Chi-Square Tests Anxiety (pre) by Occupation
Value
df
Asymp. Sig. (2-sided)
Pearson Chi-Square
20.972a
19
.338
Likelihood Ratio
28.244
19
.079
Linear-by-Linear Association
5.511
1
.019
N of Valid Cases
30
a. 40 cells (100.0%) have expected count less than 5. The minimum expected count is .40.
Table 14: Chi-Square Tests Anxiety (post) by Occupation
Value
df
Asymp. Sig. (2-sided)
Pearson Chi-Square
20.833a
15
.142
Likelihood Ratio
28.105
15
.021
Linear-by-Linear Association
.034
1
.854
N of Valid Cases
30
a. 32 cells (100.0%) have expected count less than 5. The minimum expected count is .40.
Table 15: Chi-Square Tests Understanding (pre) by Occupation
Value
df
Asymp. Sig. (2-sided)
Pearson Chi-Square
20.972a
20
.399
Likelihood Ratio
28.244
20
.104
Linear-by-Linear Association
10.629
1
.001
N of Valid Cases
30
a. 42 cells (100.0%) have expected count less than 5. The minimum expected count is .40.
Table 16: Chi-Square Tests Understanding (post) by Occupation
Value
df
Asymp. Sig. (2-sided)
Pearson Chi-Square
18.889a
18
.399
Likelihood Ratio
25.471
18
.112
Linear-by-Linear Association
4.997
1
.025
N of Valid Cases
30
a. 38 cells (100.0%) have expected count less than 5. The minimum expected count is .40.
Table 17: Chi-Square Tests Confidence (pre) by Occupation
Value
df
Asymp. Sig. (2-sided)
Pearson Chi-Square
22.708a
17
.159
Likelihood Ratio
30.337
17
.024
Linear-by-Linear Association
8.186
1
.004
N of Valid Cases
30
a. 36 cells (100.0%) have expected count less than 5. The minimum expected count is .40.
Table 18: Chi-Square Tests Confidence (post) by Occupation
Value
df
Asymp. Sig. (2-sided)
Pearson Chi-Square
17.639a
19
.547
Likelihood Ratio
23.240
19
.227
Linear-by-Linear Association
.368
1
.544
N of Valid Cases
30
a. 40 cells (100.0%) have expected count less than 5. The minimum expected count is .40.
The one way ANOVA (Table 12) shows that prior to training the difference in
anxiety means between medical and non-medical staff were significant (p=0.02), while
post-training they were not (p=0.85). The means for understanding were significantly
different before (p=0.00) and after (p=0.01) training. The difference in confidence means
for this group were significant before training (p=0.003) but not after (p=0.55).
Pearson Chi-Square tests in Tables 13-18 indicate these differences could have happened
by chance with p>0.05.
Gender
The following tables show the summed means for reported anxiety, confidence and
understanding the need for change according to participant occupation (Table 19) as well
as the ANOVA and Pearson’s Chi-Square t-tests to determine significance (Table 8).
Table 19: Summed means by gender
Female
(N=16)
Male (N=14)
Anxiety Levels
5.46
1.016
4.37
1.260
Confidence Using the Innovation
5.65
.847
4.31
1.245
Understanding Need for Change
5.80
.876
3.73
1.590
Anxiety Levels
5.46
.931
5.11
1.277
Confidence Using the Innovation
5.58
.819
4.95
1.336
Understanding Need for Change
5.48
.987
3.79
1.704
According to Table 19, prior to participating in the training program female
participants were less anxious (m=5.46) than males (m=4.37); more confident (m=5.65)
and understood the reason for the change better (m=5.80). Males reported means of 4.31
for confidence and 3.73 for understanding. After training, female participants reported the
same levels of anxiety, while males reported decrease anxiety (m=5.11). Females
indicated slightly lower confidence (m=5.58) after training, and decreased understanding
of the need for the change program (m=5.48). Male participants felt slightly more
confident (m=4.95) and their understanding for the change appeared to remain relatively
the same with a minor increase in mean (+0.06).
Table 20: One-way ANOVA by gender
Sum of Squares
df
Mean Square
F
Sig.
Anxiety
Pre
Between Groups
8.984
1
8.984
6.963
.013
Within Groups
36.131
28
1.290
Total
45.116
29
Anxiety
Post
Between Groups
.925
1
.925
.758
.391
Within Groups
34.191
35.116
28
29
1.221
Total
Understanding
Pre
Between Groups
32.038
1
32.038
20.219
.000
Within Groups
44.369
28
1.585
Total
76.407
29
Understanding
Post
Between Groups
21.413
1
21.413
11.453
.002
Within Groups
52.350
28
1.870
Total
73.763
29
Confidence
Pre
Between Groups
13.322
1
13.322
12.072
.002
Within Groups
30.897
28
1.103
Total
44.219
29
Confidence
Post
Between Groups
2.917
1
2.917
2.455
.128
Within Groups
33.267
28
1.188
Total
36.183
29
Table 20: Chi-Square Tests Anxiety (pre) by Gender
Value
df
Asymp. Sig. (2-sided)
Pearson Chi-Square
15.937a
19
.661
Likelihood Ratio
21.680
19
.300
Linear-by-Linear Association
5.775
1
.016
N of Valid Cases
30
a. 40 cells (100.0%) have expected count less than 5. The minimum expected count is .47.
Table 21: Chi-Square Tests Anxiety (post) by Gender
Value
df
Asymp. Sig. (2-sided)
Pearson Chi-Square
17.143a
15
.310
Likelihood Ratio
23.635
15
.072
Linear-by-Linear Association
.764
1
.382
N of Valid Cases
30
a. 32 cells (100.0%) have expected count less than 5. The minimum expected count is .47.
Table 22: Chi-Square Tests Understanding (pre) by Gender
Value
df
Asymp. Sig. (2-sided)
Pearson Chi-Square
23.304a
20
.274
Likelihood Ratio
32.091
20
.042
Linear-by-Linear Association
12.160
1
.000
N of Valid Cases
30
a. 42 cells (100.0%) have expected count less than 5. The minimum expected count is .47.
Table 23: Chi-Square Tests Understanding (post) by Gender
Value
df
Asymp. Sig. (2-sided)
Pearson Chi-Square
22.634a
18
.205
Likelihood Ratio
31.045
18
.028
Linear-by-Linear Association
8.418
1
.004
N of Valid Cases
30
a. 38 cells (100.0%) have expected count less than 5. The minimum expected count is .47.
Table 24: Chi-Square Tests Confidence (pre) by Gender
Value
df
Asymp. Sig. (2-sided)
Pearson Chi-Square
19.286a
17
.312
Likelihood Ratio
26.546
17
.065
Linear-by-Linear Association
8.737
1
.003
N of Valid Cases
30
a. 36 cells (100.0%) have expected count less than 5. The minimum expected count is .47.
Table 25: Chi-Square Tests Confidence (post) by Gender
Value
df
Asymp. Sig. (2-sided)
Pearson Chi-Square
19.152a
19
.447
Likelihood Ratio
26.408
19
.119
Linear-by-Linear Association
2.338
1
.126
N of Valid Cases
30
a. 40 cells (100.0%) have expected count less than 5. The minimum expected count is .47.

One way ANOVA (Table 19) tests for gender illustrate that prior to training both
anxiety (p=0.01) and confidence (p=0.002) means were significantly different between
males and females. However, after training anxiety (p=0.39) and confidence (p=0.13)
means were not significantly different. Means for understanding the need for change were
significantly different between genders both before (p=0.00) and after (p=0.002) training.
An examination of Pearson Chi-Square tests (Table 20-25) indicate that any significance
established in the ANOVA could have occurred by chance (p>0.05).
Independent samples t-tests
The researcher also ran independent samples t-tests to determine significance
between participant groups and their reported anxiety, confidence and understanding.
These tests yielded the same results as one way ANOVA tests. Tables illustrating results
from the independent t-tests are found in Appendix F.
Qualitative Results Pre-Training
This section will examine the responses to the open-ended questions included in
the pre-training survey. These questions were used to gather additional detail about
participant attitudes toward the practice management system that would shed some light
on the quantitative results.
First, respondents were asked what three words best described their feelings about
the clinic’s upcoming change to a paperless facility. Four general trends arose from
participant responses to this inquiry: feelings of anger, anxiety, readiness, and
indifference. Within these four trends, it was possible to identify various subcategories
that shed some light on the possible drivers behind respondents’ feelings regarding the
change initiative.

Some participants identified having a positive response to the implementation of a
new computer system. Responses included: “good,” “glad,” “happy,” “excited,”
“optimistic,” “needed,” “important,” “necessary,” and “positive.” Within the positive
responses to the change, participants identified reasons for their optimistic attitude. They
identified an understanding of the need for the change, citing expectations of a “current,”
“innovative,” and “modern” program that would result in “decreased overload,” improved
workflow and “better patient care.” One participant called the innovation a
“light at the end of the tunnel.”
However, it is important to note that not all participants had positive feelings
about the practice management system and not all of those who identified positive
feelings toward the innovation felt fully prepared to undergo the change. One participant
said, “I have a busy office and learning something new along with doing your daily work
is hard, but after we get used to this, I think it will be great.”
Prior to receiving the training communication, participants said they felt anxiety
and concern regarding the change effort. Responses included: “anxious,” “nervous,”
“worried,” “concerned,” “uncomfortable,” and “unsure.” Much like before, responses
were grouped into subcategories that helped identify the drivers behind the anxiety. Time
constraints were among the reasons for concern. As with those who felt that the
innovation would improve workflow, there were others who worried that learning new
procedures would be “very time consuming,” affecting workflow and, as a result, patient
care. Among his questionnaire responses one participant expressed how he felt the
innovation would affect his responsibilities, “slowing down my work, more things for me
to do.”

Still, others identified feelings of anger, resentment, and resistance toward the
practice management system. Some of the terms these individuals used to describe their
feelings toward it included: “bad,” “inefficient,” “terrible,” “worthless,” “frustrating,” and
“fear.” Upon closer look, these individuals also provided some insight into why they felt
this way. Some participants felt the change effort was chaotic and disorganized, which
would correlate with their negative view of the change. Others stated the change was
unnecessary (“needless”) — in stark contrast to the individuals who felt the clinic was
due for a change that was “modern,” “innovative,” and “current.” However, as one
participant pointed out “change is always reluctant” and there will always be individuals
that would rather keep things the same.
Finally, respondents also indicated indifference toward the change effort. Stating
they were just fine or did not know how they felt.
Next, participants were asked to identify any concerns they had regarding the
change effort. This question was designed to provide insight into the feelings that
participants identified in the previous question. The majority of respondents identified at
least one concern regarding the practice management system and only a small number
stated they had no reservations regarding the upcoming change. Those who declared
entirely positive feelings regarding the change tended to have no concerns; however,
there were still some of those who had worries.
As identified in the previous question, participants had concerns regarding time
constraints related to the innovation. Among them were the following: concern the
program would take too long to learn, cause a slow transition into the new system, and
result in too much time consumed in seeing and evaluating the patient which disrupts the

workflow. One respondent felt “it [would] take too much time to see and evaluate
patients.”
Time concerns went hand-in-hand with concerns regarding efficiency and patient
care. There was anxiety related to how the new computer system would affect the
timeliness of patient care and volume and whether it would have a negative effect on
doctor-patient relationships as a result of depersonalization. One respondent said, “I am
concerned about its effects on throughput, patient relations (too much time spent on
computer rather than patient) slowing [the] patient care process.” It appears employees
were concerned that the new computer system would require they spend more time
entering data into the system and less time speaking with the patient and devoting the
necessary one-on-one time that develops the doctor-patient relationship.
The next area of concern was related to technological difficulties and information
sharing. Participants were worried about what to do in the event of technological
difficulties such as system failures and how they would affect workflow and patient care.
They demonstrated concerns about “misinformation,” system security, “lost information,”
a lack of information sharing and with learning a new computer system.
Participants were then asked how they first heard about the upcoming change
effort in order to identify the primary form of communication regarding the change with
employees. Many participants indicated that they first heard of the change in meetings
with their supervisors, management, the board, or the CEO. Others indicated they heard it
from their peers and the grapevine, while others said they received one-way
communications such as memos and emails.
They were also asked to identify the different types of communication they
received about the change initiative prior to implementation. Participants cited verbal

forms of communication most often, indicating that the organization primarily used
twoway forms of communication, among them: information received at board meetings,
meetings, from supervisors and training classes and sessions. Others identified written or
one-sided forms of communication such as booklets, pamphlets, memos, mailers, and
literature. There were several participants who indicated they did not receive any form of
communication and others who commented on the time lapse between communications
and implementation. For example, one participant said, “[I] received communication but
it was very slow starting, so when we did start to [implement] the system, most had
forgotten.”
Participants were asked whether they felt the change initiative was necessary and
why they felt that way. Responses indicated that a large number of respondents felt the
change was needed at the medical facility. So, although many respondents have indicated
anxiety and concerned feelings regarding the change initiative, they demonstrated some
understanding of the reason behind the change, and that the reason is not without merit.
Responses included the following: the ability to provide improved service and care to
patients, improvements in obtaining patient records, the need to keep up with technology
(“keep up with the times” and “all systems will eventually become paperless”), the ability
to advance clinical research (“allow for clinical research”), and time-saving qualities.
However, there were still a number of individuals who indicated resistance to the change
initiative. Many of these individuals did not elaborate, simply saying “no,” they did not
feel the change was necessary. One respondent said, “Maybe. I have been told, but am not
convinced that there is a positive setup in patient care and management.” A lot of
participants indicated that the training program was needed in order to help them feel
more comfortable using the computer system.

Finally, participants were asked to speculate on whether they felt there was
anxiety related to the change effort in their department and what they thought was
causing it. Respondents indicated that there were anxiety issues resounding in their
departments. Some of the reasons given for this were fear of the unknown and concerns
regarding their ability to properly use the new computer system. One participant said,
“Some people are not feeling they can do it.” Another participant said, “Everyone is
worried about their role and its effect on their daily tasks.” Other concerns included the
failure to provide information and loss of data; effects on workflow (“nervous about time
consumption”) and patient care.
Qualitative Results Post-Training
After the training program, participants were asked another series of questions to
gauge if the training was effective in reducing any anxiety or resistance participants had
regarding the new computer system and provide additional detail to the post-training
quantitative results.
First, participants were asked to identify any concerns with the new computer
system that were not covered during the training program. Most participants stated they
had no concerns without elaborating, and others simply did not answer. However, of the
individuals who identified concerns the trends were related to the following: workflow
and responsibility, patient care and experience (“How will it affect patient flow and
volume [?]”), time, and technology. As with the concerns encountered prior to undergoing
the training program, individuals were concerned that the new system would affect
workflow because they would have difficulty going through their everyday tasks and as a
result patient care would suffer. Time concerns were also present, as they were prior to
the training, although it was not mentioned as much as before the training program.

Finally, there were still participants who indicated concerns regarding technological
difficulties, mainly, how to address patient care and daily tasks in the event of a computer
malfunction. As one participant put it, “How will we take care of patients when the
computer is down?”
Then, participants were asked what three words best described how they felt about
using the new computer system on a daily basis. As with the questionnaire administered
prior to the training program, several trends arose. Among them were: confidence and
comfort, anxiety and worry, and frustration.
Many respondents indicated they were happy with the computer system after
undergoing the training program. Responses included “comfortable,” “relaxed,”
“confident,” “excited,” “convenient,” “modern,” “interesting,” “hopeful,” and
“necessary.” One respondent said, “I like [the practice management system], I am looking
forward to going paperless.” Some stated they understood the programs’ timesaving
qualities, referring to it as “convenient [and] time saving.”
However, not everyone felt comfortable moving forward. There were still
respondents who indicated they felt anxious about using the new computer system.
Responses included worried, “still fearful,” confused, “apprehensive,” and
“overwhelmed.” From responses, it could be determined that some of the anxiety
individuals felt had to do with their feelings that using the program would take up too
much of their time and that it ran slowly. “Too slow (I find the computer freezes up),” one
participant pointed out.
Participants were next asked if there was anything they would change about the
training program and, if so, what it would be. A lot of respondents stated they would not
change anything about the training program. Of the individuals who felt otherwise, they

stated a need for additional time in training, or one-on-one time to facilitate
understanding and comfort.
Finally, participants were asked if there was anything they would change about the
communication they received regarding the change initiative prior to implementation.
Although most participants said no, some indicated they would have preferred more
oneon-one time and clearer communication. One participant said, “Even though there was
plenty of communication [it] was somewhat confusing and unorganized with too many
changes.”

CHAPTER 5
Discussion
This research study set out to determine the effectiveness of a training
communication at a Florida medical facility in acclimating participants to its upcoming
change to a paperless facility. The training program was intended to instruct participants,
with a specific focus on the medical staff, on how to use the new practice management
system.
This section addresses the hypotheses and research questions set forth in this
study in light of the results shown in the previous chapter. It will discuss whether the
training communication functionally reduced participant anxiety toward the change,
increased participant understanding of the need for the innovation, and increased
participant confidence using the practice management system. Additionally, trends in
qualitative responses to the open-ended questions will help determine whether
participants viewed the change as an organizational improvement, if the training
communication helped change participant perception of the change, and if it increased
change acceptance and reduced resistance. It will also address how the training program
affected the different participant groups (occupation, age, gender).
Hypotheses
H1: Communication training reduced participant anxiety about the change. As
shown in the previous chapter (Table 1), participants reported a higher mean for
anxiety (m=5.30) after training, indicating they felt more comfortable and less anxious
about the upcoming change. A paired t-test (Table 2-B) shows the change in mean was
approaching significance (p=0.06); however, H1 is rejected.

According to means for individual questions (Appendix D, Table 30 and
Appendix E, Table 39), after training participants were slightly more comfortable
adopting the practice management system (+0.56), likely because they were satisfied with
the training (m=5.00) as they felt they were able to ask questions freely (m=6.03),
making training user-friendly (m=5.80). As a result, participants believed they were more
likely to use the practice management system after undergoing training (m=5.60) H2:
Communication training increased user understanding of the need for the innovation.
Table 1 shows that overall understanding about the need for the change decreased
after the training program by 0.14. But t-test results indicate that the decrease in mean
is not significant (p=0.50), therefore not illustrating a change in attitude.
Consequently, H2 is rejected.
Still, it is interesting to note that this is the only theme for which the training
program had the opposite effect as intended (although that effect was relatively
minor). The means for anxiety and confidence had positive movements, as predicted,
while understanding means shifted in the opposite direction from what was
anticipated.
The training program did not appear to address the innovation’s potential benefits,
instead focusing more heavily on system usage. Accordingly, it did not appear to
illustrate how the changes might help streamline work and improve efficiency.
Instead, while participants viewed the change as “modern” and “convenient” (as seen
in qualitative data) they did not seem to link these qualities to the innovation’s
benefits. They were more concerned with the amount of time it would take them to
feel comfortable using the system to fully consider its advantages in the long run.
They were focused on how workload would be affected while they became

accustomed to the changes. Some felt that it would take too much time to input data
(“time-consuming,” “too slow”), or get used to the changes and therefore slow them
down. This can account for the lower means, which can be seen pre- and post-
training for the statement, “I understand the need for this change.” Prior to training,
participants had a mean of 5.57 (Appendix D, Table 29) and after it was 5.40
(Appendix E, Table 38).
It is possible that these benefits will reveal themselves over time, once use of the
practice management system has become second nature and it is easier to step back
and see the big picture.
H3: Communication training improved levels of confidence using the innovation.
While Table 1 shows there was a positive increase in participant reported
confidence means, this change was not significantly different (p=0.14), which suggests
there was no marked change in attitude. As a result, H3 is rejected. The change in mean
could have resulted by chance.
As seen in Appendix E, Table 40, participants were satisfied with the training
(m=5.00). It covered information pertinent to system usage (m=5.40), was useful
(m=5.80) and the trainer provided appropriate feedback (m=5.63), resulting in
participants believing that others would benefit from undergoing training (m=5.90).
However, this did not seem to make participants significantly more comfortable with the
innovation. While they felt the program was user-friendly (m=5.60), they were not as
secure about their ability to use the practice management system with little assistance
(m=4.97) or fit it easily into their daily work routine (m=4.53).

Research Questions
This section addresses the research questions proposed for this study by
examining quantitative results for the total group of participants along with qualitative
data gathered from the survey’s open-ended questions.
R1: How did the training communication affect participant groups (occupation, gender,
age)?
Pearson Chi-Square tests in Chapter 4 show that pre- and post-training
significance and similarities observed within groups could have resulted by chance
(p>0.05), making it difficult to identify if the changes in means occurred as a direct result
of training. As a result, the following discussion on the potential effects of training
according to participant groups is based in speculation.
Younger participants (under age 41) did not seem to benefit very much from the
training program, as their means for anxiety, confidence and understanding remained
relatively the same after undergoing training. Participants over 40, on the other hand,
reported shifts in their anxiety, confidence and understanding.
Before training, anxiety levels between these two groups were significantly
different, while after training, t-tests indicate they are not (p=0.07). This seems to imply
that the reported anxiety levels after training were similar, thus training appeared to
reduce older participants’ anxieties and bring them to a level that approached those of
younger participants (who reported little anxiety to begin with). However, confidence and
understanding remained significantly different both before and after training. While older
participants reported higher summed means for confidence (+0.40), younger participants
felt significantly more secure moving forward. This could be because younger
participants are more accustomed to using technology, as they have been exposed to it

more often during their work. Younger participants were more likely to be a part of the
office staff, and their jobs require they use the current computer system with more
frequency than the medical staff to schedule patients, requests lab tests, etc. Additionally,
younger individuals are more likely to be dexterous with technology as they, in a sense,
grew up with it.
Summed means for understanding the need for the change decreased (-0.14) for
participants over 40, moving them farther from younger participants. The training focused
more on the innovation’s usage. As discussed earlier, qualitative data indicated that
participants were focused on the amount of time if would take them to feel comfortable
enough with the new system and how this would affect efficiency and workflow in the
meantime. It is possible that because of these concerns, participants were not able to
focus on the long-term benefits, once using the practice management system became
second nature. As a result, they felt they understood the reason for the change less (with a
summed mean slightly better than neutral m=4.19). Younger participants felt relatively
confident before and after training. Upon closer inspection (Appendix E, Table 35) they
felt they understood the need for the change (m=6.00) and agreed that changing to a
paperless clinic would benefit the clinic (m=5.36), patients (5.36), and their relationship
with patients (m=5.64).
When summed means for anxiety, confidence, and understanding are observed
according to occupation, we see that the medical staff reports decreased anxiety, and
increased confidence and understanding after training, while “other” participants report
increased anxiety, and reduced confidence and understanding. Prior to training, the means
between the medical staff and “others” were significantly different. This significance
remains for confidence and understanding after training, but not for anxiety. It appears

that “other” participants over estimated their ability to learn and use the system, and the
training adjusted their expectations.
Finally, the researcher checked for any differences in summed means according to
participant gender. Females had significantly higher means than males for all measures. A
closer look revealed that all male participants were physicians, the group the medical
facility knew would be the most resistant, as they have the least interaction with the
current computer system and thus would have to change their daily routine the most. This
explains their relatively low summed means, which at their highest were only slightly
better than neutral. The training appeared to benefit males and not females. After training,
male summed means for anxiety increased to where they were no longer significantly
different than females’ anxiety summed means (which remained the same after training).
Males also reported increased summed means for confidence, while females’ confidence
means decreased. However, it seemed the training simply adjusted female expectations,
as their confidence levels remained high (m=5.58). When it came to understanding the
need for the change, the training appeared to affect females as opposed to males. The
men’s summed means remained relatively the same (+0.06) while the women’s dropped
by 0.32.
These results appear to indicate that the training was more successful with specific
groups. Members of the medical staff, which predominantly over 40 years of age and
male (all male participants were physicians), appeared to benefit the most from the
training program. This could have something to do with the fact that the training was led
by another member of the medical staff, specifically a physician. This individual may
have served as a change agent for these specific groups, as he is a trusted peer, and likely
speaks their “same language.” Additionally, the medical facility anticipated these groups

would pose the most difficulty, as they would have to adjust the most to the change.
Therefore, it appears that the training specifically focused on their needs, which could be
why there were no large changes in summed means individuals who were not members of
this group, which included most females and participants under age 41. Further research
on tailoring training to specific groups could yield interesting results.
R2: Did participants in the training believe the training functionally reduced anxiety
and improved acceptance of the change?
Quantitative data indicated that, overall, participant’s experienced a reduction in
anxiety, although t-tests indicated that the reduction was only marginal (p=0.060).
Based on quantitative data, the training helped reduce participant anxiety by
increasing their confidence using the practice management system. It also demonstrated
that all participants felt positively about the training they received.
In the qualitative data, a decrease in resentment and anxiety was observed,
although it was not fully alleviated. This could account for some of the decreases in
means observed in the age group analysis and some of the areas where the mean increases
were not very considerable.
The resistance and anxiety that were identified in the qualitative responses were
related to: concerns about time constraints, work disruption, technical difficulties,
learning a new computer system, and misinformation.
The training program appears to have provided sufficient information for some to
reduce anxiety related to the usage of the practice management system, but didn’t seem to
address other areas of concern. This was confirmed in the qualitative data when
participants were asked if they had any concerns about the computer system that were not
covered in the training program. A large portion said they had no concerns. The

participants that identified concerns said they were concerned with the time it would take
them to feel comfortable using the system (“difficulty getting tasks completed”) and how
this would affect workflow (“How will it affect patient flow and volume [?]”). Another
concern was how to address patient care and workflow in the event a system failur. As
one participant put it, “How will we take care of patients when the computer is down?”
All of this explains the quantitative results, where the group reported reduced comfort
with the amount of time they were given to prepare for the change and some participant
groups experienced decreases in anxiety variable means. They did not feel the training
addressed all of their concerns, or maybe for some, training brought concerns to their
attention they had not considered.
Respondents did seem somewhat more open to the clinic’s change after training,
with a much larger set of positive responses including, “comfortable,” “modern,”
“hopeful,” and “modern.”
Overall, the group experienced favorable changes in anxiety and confidence
variables, and reported less anxiety and resistance in the post-training open-ended
questions. The training appears to have functionally (although marginally) reduced
anxiety and resistance. However, it is important to note that participants were not
completely sold on the innovation. While they were more comfortable with using the
practice management system, they did not emerge from training as new-found supporters;
as can be seen in both qualitative and quantitative data. They still felt “concern[ed],”
“anxious,” “nervous,” and “overwhelmed,” but these emotions were mixed, as some of
these same individuals said they were “hopeful” and “excited.”
R 3: How did participants perceive the change?

Qualitative and quantitative data demonstrated that participants were divided
about the upcoming change prior to the training. There were some who were ready for the
change and simply wanted instruction on how to use the new computer system. These
individuals felt “positive” about the change; that it was “needed” and “modern … [and]
convenient.” Some were slightly against the change because they were nervous about
how to use the practice management system or whether it would be beneficial. One
individual said he was “optimistic” but “apprehensive” and found the change
“frustrating.” And others were in complete opposition, saying that it was “worthless,”
“terrible,” “bad,” “inefficient,” and could result in depersonalizing patient care. As stated
in Chapter 4, one individual said, “I am concerned about its effects on throughput, patient
relations (too much time spent on computer rather than patient), slowing patient care
process.”
After the training communication, quantitative data indicated a positive
movement in participant attitude about the change, but qualitative data indicates the
movement represents varied degrees of acceptance. The individuals who were already
proponents of the change, but were unsure how to use the innovation, had an improved
outlook about the change. They said it was “convenient,” “modern,” and “necessary.”
One participant said it was “cost effective, efficient, [and might] decrease overload.”
Those who were concerned and apprehensive about the change because of their concerns
with using the system had mixed results as did the ones who were in complete opposition.
For the former, some perceived the change as necessary once they learned how to use it.
One participant described it as “user-friendly, [and] necessary.” Others had new concerns
once they finished training like, “Will patient value decline [?].” They felt more
comfortable with using the practice management system, but were concerned about

computer failures and how that would affect workflow (“difficulty getting tasks
completed”) and patient care.
The same happened with the participants who were against the change altogether.
Some reported they were still unsure but hopeful. These individuals were concerned with
the time it would take them to feel comfortable and how that would affect patient care
and workflow in the meantime. One participant said he felt the system was “complicated”
and would “take excessive time.” There was also a concern for technology glitches. And
finally, others were simply not convinced. One said, “Half of my job duties I have yet to
understand.” They remained resistant.
R 4: Were the changes viewed as organizational improvements?
Quantitative data indicated a decrease in participants’ understanding for the need
to change to a paperless system. While some participants still indicated they understood
the need to change, they were not as confident in the practice management system’s
benefits as they were prior to training. It is likely that these individuals gave the practice
management system more credit than due, and when they actually used it in training, they
had more realistic expectations.
While some felt the innovations was “modern” and “convenient,” it is possible they
have not fully considered the long-terms benefits once everyone was comfortable with the
changes in place. And this can account for the lower quantitative means related to the
innovation’s benefits. After all, participants had some concerns about how long it would
take them to learn and be comfortable with the system and how that might negatively
affect workflow during that time. Some felt that it would take too much time to input
data, or get used to the changes and therefore slow them down.

Since the quantitative data puts the means above neutral, and qualitative data
indicates some acknowledgement of the benefits the innovation would potentially realize,
it can be said that participants viewed the change as an organizational improvement. But,
it is important to keep in mind that this view was only superficial.
CHAPTER 6
Conclusions
The size of the sample population taken for this study is not sufficient to
generalize results to the medical facility’s employee population, nor to the population at
large for that matter. However, survey results can be looked at to see how well they line
up with organizational change theory and communication theory. One of the most
evident findings is that although organizational and communication change theories
espouse the importance of communication, it is important not to regard it as some sort of
magical cure-all. Overall, participants indicated reduced anxiety and increased
confidence using the innovation, but on the whole the changes were not dramatic. This
not only shows that communication is not a magic remedy, it also demonstrates that it
must exist over time, as opposed to one allencompassing communication session. It is
not possible to cover everything in the necessary detail without overwhelming those
receiving the information.
It is evident that medical facility’s training program was not able to do it
all. Participants’ understanding of the need for the change decreased after undergoing
training. While the change was not significant (p>0.05), the fact that there appeared to be
no change in attitude about the innovation’s relative advantage merits mention. As
discussed earlier, Rogers’ Diffusion of Innovations theory (195) considers understanding

an innovation’s relative advantage a main driver in bringing individuals around to
accepting change rather than resisting it. Seeing as individuals felt less confident
regarding the need or benefits the practice management system would bring after training
indicates there is still work to be done. Without this component, the medical facility will
continue an uphill battle against change resistance because its members will continue to
search for meaning, as uncertainty is still present. “Individuals are more likely to adopt an
innovation if they think it will help them” (Berwick, 2003, p. 1971).
Because the training program focused more on innovation usage, and was somewhat
successful (marginally) in reducing anxiety, it is possible that continued communication
about the practice management system and prolonged exposure and usage will help
participants better understand the innovation’s relative advantage and as a result the reason
for the change initiative. According to Roger’s (1995) Diffusion of Innovations theory, this
is known as the clarifying stage in the initiation phase. It occurs when an innovation is put
to use in an organization so that the innovation’s meaning becomes clearer to its members.
It consists of a “social construction.” “When a new idea is first implemented in an
organization it has little meaning to the organization’s members,” which is what appears to
be happening in this particular case (p. 399). This research only focused on the training
communication, and as a result it is not possible to draw conclusions about any additional
communication participants may have received. This is considered a limitation of this
study. Perhaps a longitudinal study would indicate a change in participant attitude regarding
the organization’s change effort. It would be interesting to see if anxiety and confidence
continue to benefit over time, and whether time will also play a significant factor in
exposing the innovation’s relative advantage.

That being said, this research study does not discredit the importance and necessity of
communication in change facilitation. Study participants, in their qualitative responses,
indicated that they would benefit from additional one-on-one sessions or more
individualized training sessions (“more one-one-one”). This goes hand-in-hand with
findings from Goodman and Truss’s 2004 study, where employees indicated a preference
for two-way communication.
Moreover, participants responded positively to the training they received, as
illustrated by quantitative data (Appendix E). It is because of this that this research
concludes that the training communication was somewhat useful and beneficial.
Participants strongly felt that others should take part in the training course. However, it is
simply not possible to address a large change effort during one training session. As one
participant stated, “[We] should have training over several sessions.”
Another training program attribute that merits mention, is that it was led by a member
of the physician staff and not a representative from the software company that provided
the innovation to the medical facility. It was evident from interaction in the training
sessions that participants felt comfortable around the doctor who provided the training
and regarded him a knowledgeable individual. There were no negative responses related
to the training program and its facilitator’s ability to communicate information to
participants (Appendix E).
The medical facility employed a change agent as the face of the training program
supporting the practice management system. However, it would have likely benefited
from employing more than one change agent. Not doing so places too much responsibility
on one individual and increases chances for failure. Moreover, having more than one

individual advocating this change would have provided participants additional people to
turn to with questions, and would lend the change effort more credibility.
Another approach that may have been beneficial was to train a group of individuals
through implementation before rolling the change effort out to the entire staff. Rogers
(1995) referred to this as observability. If the change effort is successful in one
department, and remaining organizational members are able to observe this success, they
are more likely to be receptive to adopting the innovation as well. Furthermore, rolling
out a change effort in one department before doing so in the remainder of the organization
can help with strategic planning. Organizations are able to identify pitfalls and work to
address them before implementing a change throughout. By not employing this method,
the medical facility’s change effort seemed haphazard. Training sessions were postponed
for long periods of time while the organization addressed roadblocks, which did not go
unnoticed. In the qualitative section of the research, one individual pointed out that from
start to implementation the change effort “was very slow starting so when we did start to
[implement] the system, most had been forgotten.” Another individual said, “Even though
there was plenty of communication, the communication was somewhat confusing and
unorganized with too many changes.”
Overall, the training program was minimally successful in reducing anxiety, but did
not increase confidence and participant understanding of the need for the change.
The researcher encountered some limitations in her study. The small sample size
made it difficult to draw a better understanding of participants’ view of the change and
training. The medical facility’s training session postponement added to this limitation.
The researcher had difficulty staying informed of when training would restart, and missed

training sessions that would have made it possible to collect additional survey
questionnaires.
As mentioned before, having only studied the training communication program also
limited the conclusions that could be drawn. This study may have benefited from a
longitudinal component that would have identified the effect of time and exposure to
change acceptance or resistance.
Additionally, there is an opportunity to expand and focus this research specifically
into the field of public relations, to emphasize or study the need for tailored and strategic
communications to enact successful change efforts. While this study focused on the
training communications directed at a small group, an extension of this research could
include the study of multiple communication vehicles, seeing as two-way and one-on-one
communication is often time consuming and not always feasible. A study such as this one
could shed additional light on effective communication tools during different
facets/stages of a change program. As a participant in this study pointed out, the
communication received outside of training from the initial announcement of the
upcoming change to the change implementation was sporadic, and made the effort seem
haphazard. What types of communication efforts would have helped alleviate this? When
is one-way communication more effective than two-way communication? How much and
what types of communication vehicles are best employed when?
Also, expanding the sample size or possibly extending the research over multiple
hospitals or medical facilities could yield generalizeable results, especially considering
the continued increase in the use of technology in the workforce. As more medical
facilities switch to electronic practice management, what opportunities exist for training?

This study showed a marked difference between medical staff members and
nonmedical staff members regarding their comfort, understanding and anxiety related to
adopting the change to a paperless facility. The training communication appeared to
resound more effectively among the medical staff than others. This supports a closer look
into the need for strategically-tailored training and communication approaches for
specific audiences. Would individuals who were not members of the medical staff have
benefited from different forms of training? Would they have needed less one-on-one? Was
their training jeopardized by those who were not as advanced as they were with the
computer system? What is it about training programs that make them resonate better for
some people than for others? Further research on this topic may yield interesting results.
Yet another area that merits investigation is the appropriate development of
interactive, multimedia training programs. As stated earlier, two-way communication, or
one-on-one training is time-consuming and in this day and age not always viable. How
can training communication work effectively in the digital age? How much can be taught
through software programs and what needs additional attention from trainers?

