



ABS 394: Food and Human Health - Content Guide Instructor: Dr. Oya Yazgan
Subtopic 4A
1
Subtopic 4A: Diseases involving the
digestive system
In the previous module we talked mainly about
our hormonal responses to consumption of food.
These responses take place similarly in humans
and other related animals since they involve
major metabolic pathways that form the
backbone of our physiology and are highly
conserved. Disturbances in these hormonal
responses, mainly caused by eating excessive
amounts of foods we are not adapted to eat, can
lead to development of serious chronic illnesses,
such as diabetes and cardiovascular disease. We
will talk more about these illnesses in the next
subtopic.
In this subtopic, we will concentrate on other
reactions that are triggered by ingestion of
certain foods by some people and on their
influence mainly on the digestive system. These
are negative reactions that are not common to
everyone and can be triggered by different
components of foods that many other people can
tolerate without any obvious problems. So, why
are some people susceptible and others aren’t?
There are many different thoughts on the causes
of these ailments and plenty of research is being
done, but we do not have any definite answers
yet. Though there are some promising findings.
Food allergies, intolerances and sensitivities.
Some of the immediate negative reactions to
food are categorized under allergies, sensitivities
and intolerances. Watch the following two videos
for a brief introduction to the differences. The
specific types of immune cells mentioned in these
videos are not important for this course, just
remember that they are part of our immune
defenses and take part in these allergic reactions.
4A-1 [Video]: Differences between food allergies and
intolerance
4A-2 [Video]: Understanding food allergies
• How is an allergy (Type 1) defined?
• What are common symptoms of food allergies?
• Which antibody is involved in food allergies?
• What is anaphylaxis? What are the symptoms?
• What are some causes of food intolerances or
sensitivities? What antibodies are usually involved
in food intolerances/sensitivities?
• How long can it take for food intolerances to
display symptoms? How are they diagnosed?
Food allergies involve our immune system. Our
blood has many different types of cells and one
group of blood cells, referred to as white blood
cells (WBCs) are involved in many of our immune
reactions. There are also several different types
of white blood cells and some of them produce
antibodies. Antibodies are a particular type of
proteins that recognize invading foreign targets
very specifically and signal other immune cells to
Figure 1. Development of allergies after encounters
with allergens.
ABS 394: Food and Human Health - Content Guide Instructor: Dr. Oya Yazgan
Subtopic 4A
2
destroy these foreign invaders, which could be
proteins, viruses or bacterial cells that enter our
tissues. Our immune system produces different
types of antibodies for different targets and for
different locations in the body. The type of
antibody involved in typical food allergies (Type 1
or immediate-response allergy) is referred to as
Immunoglobulin E, or IgE for short, and leads to
release of histamines from specific immune cells.
Histamines are the chemicals that cause the
characteristic symptoms of allergies (see Figure
1). The most common way of testing for food
allergies is the skin test, where they inject a very
small amount of the different food components
being tested under the skin (generally on the
back) and see if redness and itchiness develops at
the injection site, which is an indication of local
histamine action triggered by the IgE-mediated
allergic immune response. Medications referred
to as anti-histamines diminish the action of
histamines, and therefore alleviate some of the
symptoms of allergies.
Why are some people prone to allergies and why
is the prevalence of allergies on the rise?
Unfortunately, there is no clear answer for the
cause, but one likely explanation involves our
favorite subject, the gut microbiota and its proper
establishment during early childhood.
The following video is a talk on studies done on
mice that were transplanted either with
microbiota from non-allergic infants, or from
those allergic to cow’s milk, in a similar fashion to
the studies involving obesity and malnutrition we
saw earlier. This is also a great review of some of
the topics we discussed regarding microbiota.
4A-3 [Video]: Food allergies and the gut microbiome
• How many Americans are estimated to suffer from
food allergies?
• What are some factors that are thought be related
to increases in cases of food allergies?
• What period of our lives is our immune system
most susceptible to damage and also to
intervention?
• What is a germ-free mouse? Why are they used?
• Research by Dr. Nagler identified a type of
bacterium called Clostridium. What two benefits
does this bacterium provide us regarding our
digestive system?
• What was the result of feeding mice that were
transplanted with gut microbiota from children
with cow’s milk allergies who were eating the
probiotic supplemented diet?
• What are some therapeutic approaches that are
being worked on regarding treatment of allergies?
This video talks about the effect of the gut
microbiota (especially the group of bacteria
referred to as Clostridia, which are common in
healthy guts) in maintaining a healthy layer of
cells lining the intestinal wall, along with the
overlaying mucus layer protecting these cells
from the potentially harmful contents of the
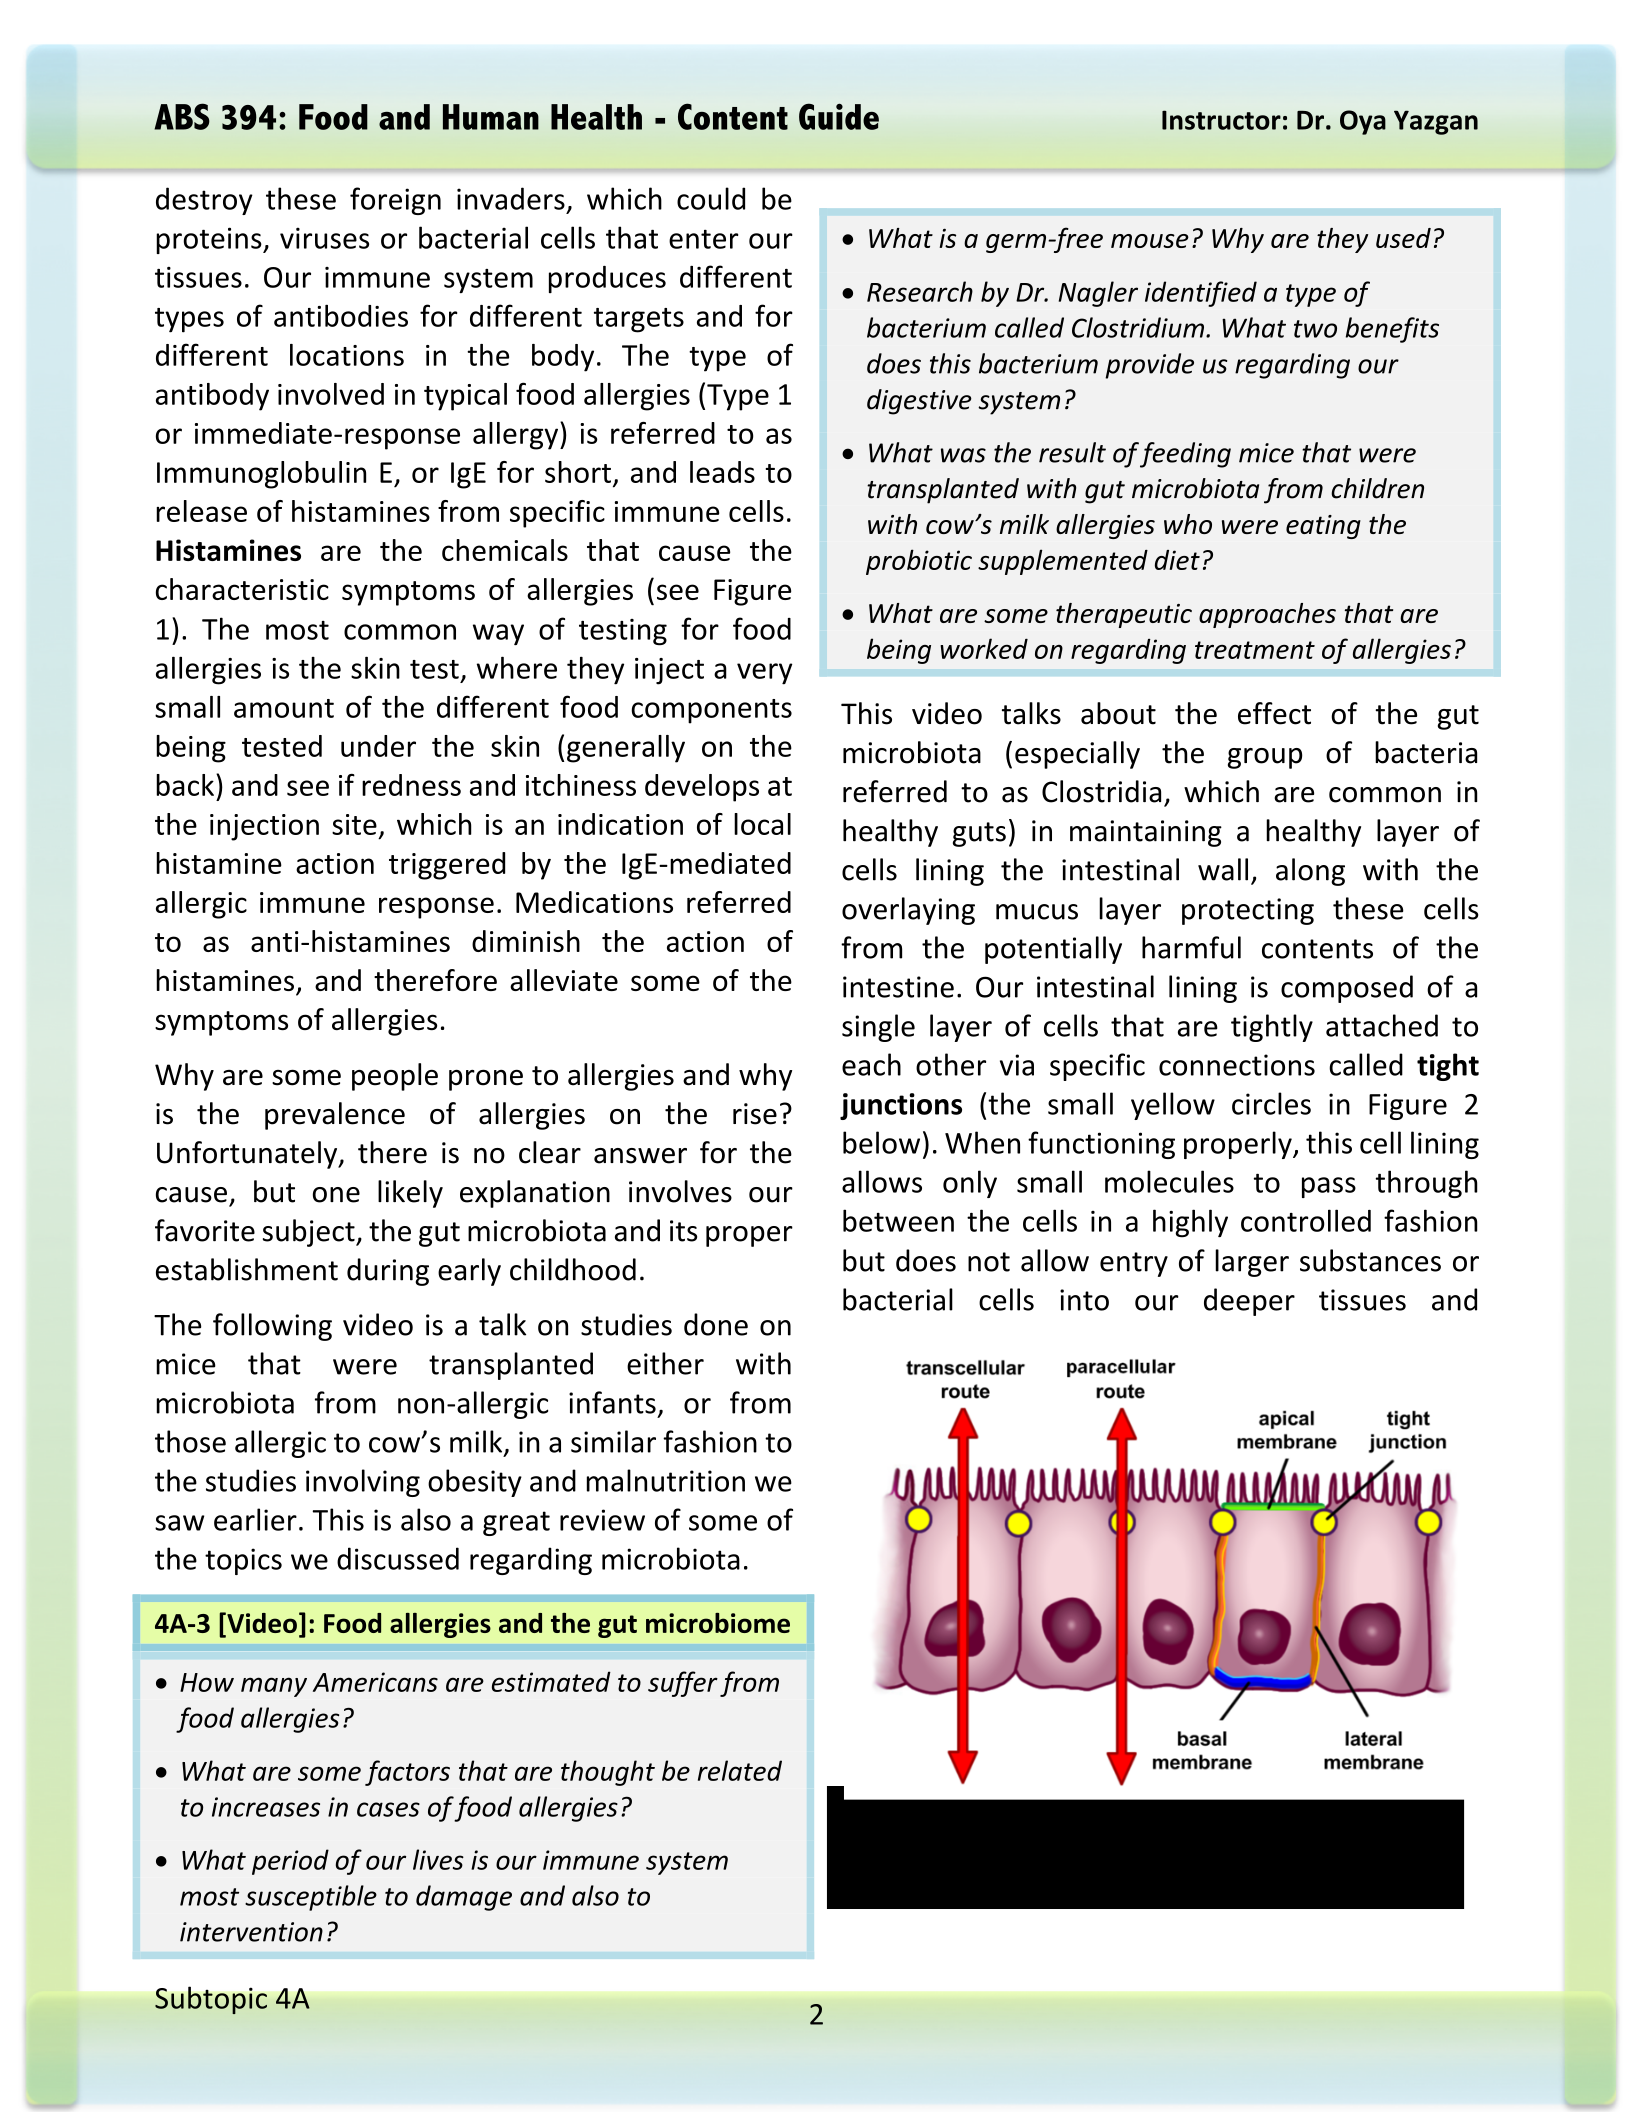
intestine. Our intestinal lining is composed of a
single layer of cells that are tightly attached to
each other via specific connections called tight
junctions (the small yellow circles in Figure 2
below). When functioning properly, this cell lining
allows only small molecules to pass through
between the cells in a highly controlled fashion
but does not allow entry of larger substances or
bacterial cells into our deeper tissues and
Figure 2. Healthy tight junctions between the cells seal
the intestinal wall and prevent leakage of the contents
into the bloodstream.

ABS 394: Food and Human Health - Content Guide Instructor: Dr. Oya Yazgan
Subtopic 4A
3
bloodstream that lies immediately underneath
the bottom surface of these cells.
However, the integrity of this intestinal barrier
can get compromised due to nonfunctional tight
junctions. When tight junctions are loosened and
cannot seal the intestinal wall, larger substances
like undigested food particles, toxins and bacteria
can pass through and get into the bloodstream,
where they do not belong (see Figure 3 below).
This condition is referred to as intestinal
permeability (or leaky gut in common language).
Any foreign substance that somehow finds its
way into our bloodstream can trigger a strong
immune reaction. This is a part of our normal
immune reaction to eliminate any foreign
substance that can potentially cause harm or
disease. Our immune systems can remember
these foreign substances for a very long time
(often for many years) and are prepared to launch
a very rapid and strong attack if that same
substance is encountered again in the future. This
is how we naturally become immune to infections
by bacteria or viruses we had in the past (like to
the cold or flu viruses) and how vaccinations
work. But in some cases, instead of us becoming
immune to (or protected against) an invading
pathogenic organism, we become reactive to
specific foods because some components of
these food particles enter into our bloodstream
through our weakened intestinal lining when they
were not supposed to and trigger a specific
immune reaction against them. Since we then
become immunized towards these substances,
any subsequent exposure to that food triggers a
very strong and specific immune response, which
is the typical allergic reactions in many cases.
Besides food allergies, we also have many food
intolerances, a very diverse group of reactions.
Some of these intolerances are caused by lack of
specific enzymes that are required for properly
digesting a food component. The following video
introduces a food intolerance probably familiar to
many: lactose intolerance. Lactose is a
disaccharide (sugar) found in dairy and is
composed of a molecule of glucose and galactose
bonded together. Lactose cannot be used by our
bodies as an energy and carbon source unless it is
broken down into its glucose and galactose
components. To be able to use lactose, we need
an enzyme called lactase, which breaks down the
bond joining the glucose and the galactose
monomers, thus making each molecule available
to our bodies.
4A-4 [Video]: Lactose intolerance
• What enzyme allows us to break down lactose and
to digest it?
• For the majority of the population, what time
period in our lives is this specific enzyme normally
produced?
• What genetic change allowed some individuals to
continue to tolerate ingestion of lactose?
Lactose intolerance is a relatively simple case that
can be explained and managed easily. People
who are lactose intolerant can simply avoid foods
containing dairy or can take over the counter pills
Figure 3. Damaged intestinal lining fails to seal the
intestinal wall and allows leakage of the contents into
deeper tissues, triggering strong immune reactions.

ABS 394: Food and Human Health - Content Guide Instructor: Dr. Oya Yazgan
Subtopic 4A
4
(e.g. Lactaid) that have the lactase enzyme when
they eat foods containing lactose and avoid much
of the temporary intestinal discomfort.
However, sometimes the reasons for not being
able to tolerate a specific food item are not so
clear. Examples of this are the problems
encountered by some people upon ingestion of
wheat. Wheat consumption can cause various
digestive or systemic symptoms in people who
cannot tolerate some component of it. It is
usually one of the proteins in the grain that is not
tolerated (typically gluten), and the resulting
negative reactions might involve very different
mechanisms.
A few people are simply allergic (Type 1 allergy)
to certain proteins in wheat, most commonly to
gluten, while others suffer from a serious
condition referred to as celiac disease. Celiac
disease is caused by a serious delayed immune
reaction to gluten, one of the storage proteins
found in wheat, rye and barley. Because of its
unique structure and amino acid composition,
gluten is partly resistant to digestive enzymes in
the intestines and these small undigested
segments of the gluten protein can cross the
intestinal lining due to intestinal permeability and
trigger the immune system. Severe immune
reactions triggered repeatedly by these gluten
fragments gradually lead to structural damage to
the lining of the small intestine. Microscopic
projections on the intestinal cells called villi (see
the small finger-like projections on the intestinal
cells in Figure 2 above) are shortened as a result
of this immune reaction and subsequently result
in malnutrition since these structures are critical
in nutrient absorption. Sometimes gluten-like
proteins in what are considered to be gluten-free
grains like rice and corn can cross-react and
trigger similar immune reactions and aggravate
the symptoms in people with celiac disease.
Yet, there are others who are not directly allergic
to wheat proteins, or do not have celiac disease,
but still suffer from digestive problems upon
consumption of wheat. This condition is usually
referred to as wheat sensitivity (or wheat
intolerance) and might also involve immune
system activation involving other types of
antibodies such as IgG and IgM instead of IgE. This
type of immune reaction shows delayed negative
effects which are different from those seen in
typical food allergies.
Other non-gluten protein components referred
to as ATIs (a-amylase/ trypsin inhibitors) in wheat
and related grains are also indicated in triggering
discomfort, immune reactions and inflammation
in both celiac disease and other non-celiac
inflammatory disorders of the digestive tract.
ATIs are specific pest- and parasite-defense
proteins in wheat and related grains. ATIs also
have the ability to inhibit the activity of our
digestive enzymes (amylase for breaking down
starches and trypsin for breaking down proteins)
and hence can make digestion of these grains
difficult for many people. High-yield, high-gluten
and highly pest-resistant wheat varieties that
were cultivated in recent years have significantly
elevated levels of ATIs and this could potentially
be a contributing factor to the recent drastic
increases we see in digestive and intestinal
discomfort resulting from wheat consumption as
well. In mouse studies ATIs also induce allergic
airway inflammation in the lungs, in addition to
the intestinal inflammation.
Watch the following video for a brief introduction
to common problems with wheat consumption.
4A-5 [Video]: Problems with wheat
• What is gluten? What is it made up of?
• What are three problems associated with wheat
consumption?
• What is Celiac disease? What happens to the
intestinal lining in Celiac disease?
• What are some symptoms of non-celiac gluten
sensitivity?
• What are possible causes of non-celiac gluten
sensitivity (or wheat intolerance)?
• What is the nocebo effect?

ABS 394: Food and Human Health - Content Guide Instructor: Dr. Oya Yazgan
Subtopic 4A
5
Wheat consumption is frequently associated with
Irritable bowel syndrome (IBS) as well. In IBS,
intestinal irritation is believed to be caused by
consumption of various foods, but the main
triggers are not clear. For a more extensive
review of IBS, you can read the optional article
“Sensitivity to wheat, gluten and FODMAPs” in
the extra materials section on Canvas. The
following video summarizes the general
characteristics of IBS.
4A-6 [Video]: Irritable bowel syndrome (IBS)
• What are two common symptoms of irritable
bowel syndrome?
• How does irritable bowel syndrome differ from
inflammatory bowel disease?
• What are risk factors for developing IBS?
Irritable bowel syndrome (IBS) is a collection of
symptoms, which tend to surface when the
digestive system is triggered by ingestion of food
or other irritating substances. On the other hand,
inflammatory bowel diseases (IBD), like Crohn’s
disease (CD) and Ulcerative colitis (UC), include a
strong inflammatory component (an immune
response involved in protection against
pathogens, damaged cells or toxins) and
generally involve lesions in the gastrointestinal
track. They are believed to be caused by exposure
to environmental triggers in people who are
genetically predisposed. Not so surprisingly,
there are identifiable differences in the
microbiota of people with IBD. For a detailed
discussion of the role of diet and microbiota in
IBD, see the extra materials section.
The condition of the cells lining our gut is a major
determining factor in the sensitivity of our
intestines to irritants. You have seen earlier that
the foods we eat have a significant role in the
composition and diversity of our microbiota.
Fiber in the diet feeds the beneficial bacteria,
which in turn produce short-chain fatty acids like
butyrate that feed our intestinal cells. Our
intestinal cells then produce plenty of mucus
which serves as a food source for some of these
beneficial mucus-foraging bacteria and promotes
diversity of the microbiota. A healthy community
of microbiota is one that cooperates with our
bodies and feeds our intestinal cells, resulting in
maintenance of protective mucus in our
intestines. This mucus layer is critical in the
barrier function of the intestinal lining. The
beneficial bacteria also protect us from
pathogens by occupying all attachment sites on
the intestinal lining, thereby not allowing any
ingested pathogens to attach and colonize. In
addition, these beneficial bacteria produce
antimicrobial substances that kill many of the
pathogens. The presence of these beneficial
bacteria and the actual mucus barrier itself
reduces infiltration of the intestinal lining by
pathogenic bacteria, food particles and toxins. In
this state, the immune activity in the intestine is
low and our cells can function optimally and
effectively absorb nutrients from foods.
We have seen before that this healthy state in the
intestines is established initially by inoculation of
the infant’s gut with the mother’s microbiota
during vaginal birth. In addition, breastfed infants
develop gut microbiota that induces a tolerant
immune system and reduces the risk of pathogen
colonization, infection and gut inflammation.
Remember the HMOs (human milk
oligosaccharides) in breast milk and colostrum?
Interestingly, these HMOs have a very similar
molecular structure to the mucus produced by
the intestinal cells and promote growth of the
future beneficial members of the microbiota.
When the infant stops nursing and consequently
the HMOs are no longer available, these bacteria
simply shift to feeding on the structurally similar
mucus and get established as beneficial members
of the microbiota. Furthermore, some breast milk
fats are converted to antimicrobial compounds in
the infant’s gut, which kill many pathogenic
bacteria and fungi, thus only allowing beneficial
bacteria to colonize the intestines of the infant.
This is mainly why vaginal birth and breastfeeding
is thought to be protective against development
of allergies later in life.
ABS 394: Food and Human Health - Content Guide Instructor: Dr. Oya Yazgan
Subtopic 4A
6
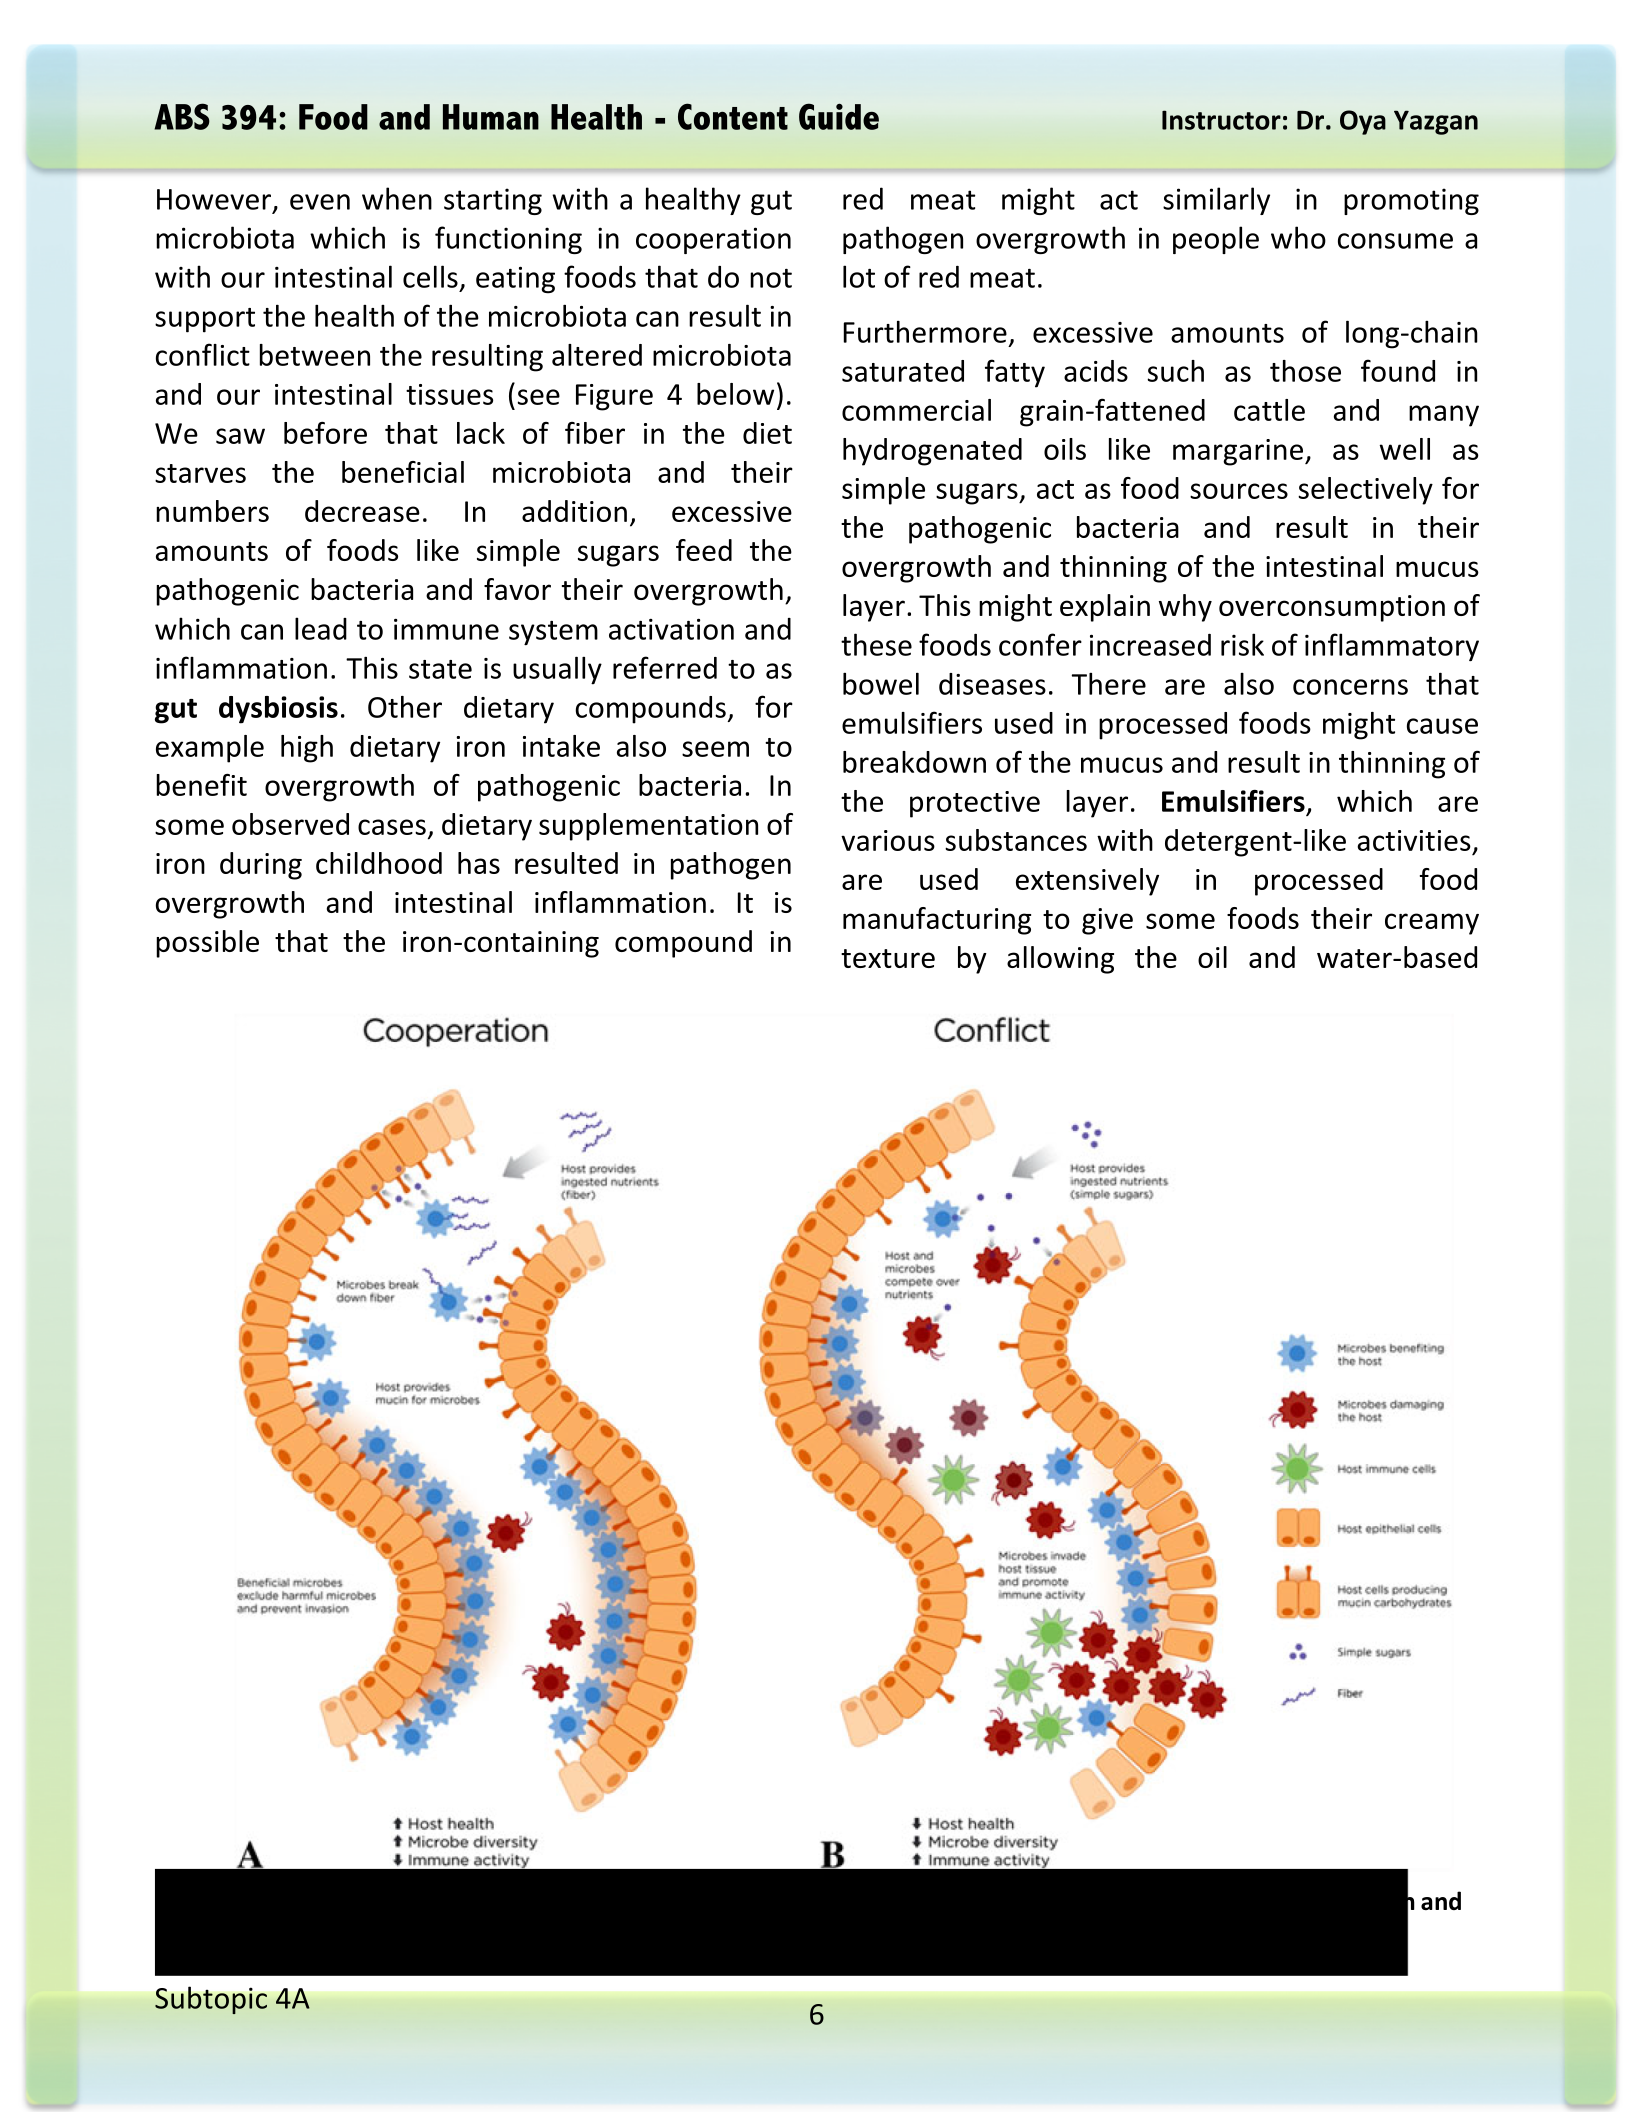
However, even when starting with a healthy gut
microbiota which is functioning in cooperation
with our intestinal cells, eating foods that do not
support the health of the microbiota can result in
conflict between the resulting altered microbiota
and our intestinal tissues (see Figure 4 below).
We saw before that lack of fiber in the diet
starves the beneficial microbiota and their
numbers decrease. In addition, excessive
amounts of foods like simple sugars feed the
pathogenic bacteria and favor their overgrowth,
which can lead to immune system activation and
inflammation. This state is usually referred to as
gut dysbiosis. Other dietary compounds, for
example high dietary iron intake also seem to
benefit overgrowth of pathogenic bacteria. In
some observed cases, dietary supplementation of
iron during childhood has resulted in pathogen
overgrowth and intestinal inflammation. It is
possible that the iron-containing compound in
red meat might act similarly in promoting
pathogen overgrowth in people who consume a
lot of red meat.
Furthermore, excessive amounts of long-chain
saturated fatty acids such as those found in
commercial grain-fattened cattle and many
hydrogenated oils like margarine, as well as
simple sugars, act as food sources selectively for
the pathogenic bacteria and result in their
overgrowth and thinning of the intestinal mucus
layer. This might explain why overconsumption of
these foods confer increased risk of inflammatory
bowel diseases. There are also concerns that
emulsifiers used in processed foods might cause
breakdown of the mucus and result in thinning of
the protective layer. Emulsifiers, which are
various substances with detergent-like activities,
are used extensively in processed food
manufacturing to give some foods their creamy
texture by allowing the oil and water-based
Figure 4. Cooperation between the gut microbiota and the intestinal cells promote gut health. Improper nutrition and
lack of fiber induce a conflicting state, leading to decreased host health and increased immune activity.

ABS 394: Food and Human Health - Content Guide Instructor: Dr. Oya Yazgan
Subtopic 4A
7
components to mix into a smooth emulsion.
Mayonnaise, salad dressings, chocolate, ice
cream and some baked goods are common food
items that include large amounts of emulsifiers.
Some emulsifiers can be found naturally in some
food sources such as egg yolks, but most are
generally synthesized using plant oils or animal
fats as the starting material and are used in large
quantities in processed foods.
The Western diet has been shown to cause
altered microbiota, mucus layer thinning and
increased bacterial density very close to the cells
lining the intestinal wall. As we have seen earlier,
in healthy individuals the cells of the intestinal
wall are covered with a thick layer of protective
mucus, which keeps the bacteria farther away
and the immune system activity low. Certain
bacterial compounds, as well as gluten, are
known to trigger a cascade of reactions in the cell
(through a protein called zonulin) which results in
loosening of the tight junctions that seal the
intestinal cells. When the intestinal barrier gets
weakened, undigested food particles, bacterial
cells and chemicals get into the bloodstream and
trigger immune reactions leading to local or even
systemic inflammation that are increasingly being
associated with inflammatory bowel disease
(IBD), celiac disease, irritable bowel syndrome
(IBS), multiple sclerosis (MS), rheumatoid arthritis
(RA), type 1 diabetes (T1D), asthma, necrotizing
enterocolitis and autism spectrum disorders
(ASD). The Western diet-induced thinning of the
mucus layer and the consequent irritation,
inflammation and immune reactions can partly
explain the recent rises in these disorders.
It is becoming more evident that systemic chronic
inflammation, meaning a low-grade immune
reaction throughout the body, is a major
contributor to many of the illnesses we are facing
today, including various autoimmune diseases.
We will look into the common features of some
of these and other chronic conditions in the next
subtopic.
Powered by TCPDF (www.tcpdf.org)

