


Running head: TEP FINAL PAPER – FIRST DRAFT 1
TEP Final Paper – First Draft
MarthaKay Farmer
Liberty University

TEP FINAL PAPER – FIRST DRAFT 2
TEP Final Paper
Introduction
The concept of emergency care is frightening, to say the least, for most patients and the
families of patients, but children seem to have a stronger perception of emergencies or
distressing situations. Though the reasoning is unclear, research has determined that children
who are in high distress or encounter an emergent event have a higher recall of the unique
aspects of the events, and the distress itself, for a longer period than adult patients who
experience high distress in an emergent event (Peterson, 2010). In addition to easy recall of
distress, when children come to the emergency room their perceptions and reactions often feed
off the child’s caregivers’ perceptions and reactions (Byczkowski, Fitzgerald, Kennebeck,
Vaughn, Myers, Kachelmeyer, & Timm, 2013; Peterson, 2010). It is, thus, imperative that nurses
keep the care of the child’s emotional needs in mind as they busy themselves taking care of the
child’s physical needs, particularly in high stress situations that are often associated with an
emergency room. The intention of this paper is to demonstrate how Watson’s Human Caring
Science Theory can be practically applied using one specific nurse-patient exemplar.
Overview of Jean Watson’s Caring Science Theory
Jean Watson’s Human Caring Science is a human interactive theory that integrates a
unitarian world view (Watson, 2018). According the Watson Caring Science Institute, the theory
“seeks to develop caring as an ontological and theoretical-philosophical-ethical framework for
the profession and discipline of nursing and clarify its mature relationship and distinct
intersection with other health sciences” (Watson, 2018, “Guiding Questions for Systems”, para.
3). A primary tenant of the philosophy of a caring science promotes that humans are holistic;
therefore, nursing encompasses caring for the physical and mental aspects, as well as a person’s

THEORY-BASED EXEMPLAR PAPER (TEP) FIRST DRAFT 3
spiritual and ethical dimensions (McEwen & Wills, 2014). The foundation of Watson’s work is
the focal ideology of a transpersonal caring relationship which is developed within the concept of
a caring occasion, also referred to as a caring moment (Watson, 2018). Watson writes that a
caring moment “occurs when the one caring connects with and embraces the spirit of the other
through authentic, full attention in the here and now, and conveys a concern for the inner life and
personal meaning of another” (Sitzman & Watson, 2014, p. 17).
Watson has defined ten caring ten fundamental Caritas Processes. The etymology of
caritas is Latin for charity or virtue that has carries a connotation of a deep, caring love;
therefore, Watson’s Caritas are essentially ten nursing virtues that are guidelines for putting her
theory into practice and action (Watson, 2008). While caring for a patient, the Caritas Processes
or nursing virtues that a nurse should employee during the caring moment are
1. Practicing loving-kindness and equanimity within context of caring
consciousness.
2. Being authentically present and enabling and sustaining the deep belief system
and subjective life world of self and one-being cared for.
3. Cultivating one’s own spiritual practices and transpersonal self, going beyond
ego self.
4. Developing and sustaining a helping-trusting, authentic caring relationship.
5. Being present to and supportive of the expression of positive and negative
feelings.
6. Creatively using self and all ways of knowing as part of the caring process;
engaging in artistry of caring-healing practices.

THEORY-BASED EXEMPLAR PAPER (TEP) FIRST DRAFT 4
7. Engaging in genuine teaching-learning experiences that attend to wholeness
and meaning, attempting to stay within other’s frame of reference.
8. Creating healing environment at all levels, whereby wholeness, beauty,
comfort, dignity, and peace are potentiated.
9. Assisting with basic needs, with an intentional caring consciousness,
administering ‘human care essentials,’ which potentiate alignment of mind-body-spirit
wholeness in all aspects of care.
10. Opening and attending to mysterious dimensions of one’s life-death; soul care
for self and the one-being-cared for; “allowing and being open to miracles.” (Wagner,
2010, p. 2).
Exemplar Experience with a Frightened Four Year Old
An example of caring practice experience within my practice involved a 4 year-old
female, accompanied by her mother, who presented to the Children’s Emergency Center (CEC)
with a chin laceration due to a fall where she collided with a tile floor when she tripped while
running at home. Upon arriving at the CEC, the child was greeted by the patient registration
personnel whose instructions are to quickly register the patient while alerting the CEC staff that a
pediatric patient has arrived. I was called to the front where I found the child and her mother
both crying – mom gently while the child was in hysterics. With a smile on my face and a
cheerful greeting, I introduced myself, confirmed the child’s name and birthdate, quickly
assessed the laceration that was hidden under a bloody towel, and began escorting them to the
room. From the moment I met the child I continually peppered our conversation with
reassurance the parent and child would be taken care of. As we walked to the child’s room, I
allowed the parent to talk, and she explained the events and expressed how she felt “awful” for

THEORY-BASED EXEMPLAR PAPER (TEP) FIRST DRAFT 5
not preventing her child from falling. Fortunately, our exam rooms are fun, scare-free places
designed with children and parents in mind, so as we entered the room, I showed mom the safety
features that are in place to prevent further falls and comfort features for her and the patient.
After the mother had recounted her story, I explained the general procedures for repairing
a facial laceration, introduced the doctor who would be working with her daughter, and described
the philosophy of care that we utilize for children. I explained that we use atraumatic care,
meaning as much as possible we work at the child’s pace; we utilize distraction agents such as
bubbles, toys, electronics, or games to reduce patient stress; we employ pain management
medication to ease the discomfort during procedures; and above all we do not aggressively
approach the child to hold them down, but rather engage the parent and child in positions of
comfort to be able to perform procedures. As the conversation with mom flowed, mom was
relaxing and no longer crying, the child followed suit and her hysterics settled to gentle tears.
At this point I turned my attention towards the child. I offered her some toys to play with
while I began the initial assessment. On my badge reels, I have Lego dolls attached, so when I
spend time with a patient, they often immediately notice my Lego toys and want to play with
them. Our unit policy is that all conversations with any patient is to occur at eye level, so my
Lego toys are usually the ice breaker. This was the case with this child, too. She would not
answer me directly but would hold the Lego dolls and talk through them. When the time came
that I was assessing the wound, I noted the patient was extraordinarily anxious, so I backed off
and asked her about her fears. She began to tell me she was afraid of “getting shots.” I took
more time to re-explain the events to her and I reassured her that neither myself or the doctor
would be using a shot on her face. I explained I would be applying a numbing gel medication,
called LET, and would let her know about each step before I proceeded. Before I went to get her

THEORY-BASED EXEMPLAR PAPER (TEP) FIRST DRAFT 6
medication, she and I sat on the bed together waiting on the doctor to arrive to the room. I
reintroduced the doctor and told her he was a very nice and kind doctor who knew how to fix
chins without hurting her and that I had trusted him enough to allow him to care for my own
daughter. As we waited approximately two minutes for the doctor to enter, she played with my
Lego dolls and the other toys that were brought to her, so by the time the doctor arrived, mom
was relaxed, the patient had stopped crying and both were willing to allow the doctor examine
her.
During the medical exam, I went to retrieve the LET and laceration repair supplies. The
LET takes at least thirty minutes to take full affect, so I applied the mediation and asked the child
about her entertainment preferences. I reminded her that she was in control of her environment
and that she could choose to play with toys or watch television, but she needed stay in the room
on the bed so the patch holding the LET in place would not come off. After answering all her
questions, her mother’s questions, and setting the timeframe expectations, I left to attend other
tasks and patients.
Our department employs a Child Life Specialist who attends procedures to help distract
and comfort patients. If a doctor expects to need a third arm, then the nurse attends the
procedure as well. In this case the doctor did not expect to need my presence, so I was not there
at the beginning of the procedure. Since I left the mother and child in a peaceful and calm state
and one of the most caring and competent doctors was on duty that day, I was quite surprised to
hear the child break into a screaming fit as the doctor approached her to do the laceration repair.
The doctor called me in and told me the child was refusing for anyone to touch her other than the
nurse. Under this hospital’s policies, laceration repair is a medical procedure to be conducted
only by medical staff, not nursing staff, although we are trained to do such procedures.

THEORY-BASED EXEMPLAR PAPER (TEP) FIRST DRAFT 7
However, this child would not allow anyone to touch her except me. The doctor asked if I would
glove up and be his third arm, so I did, and the doctor and I repaired the laceration together. The
child did not move, flinch, or tear up once during the procedure. The physician kindly offered to
do the area clean up, so that I could go and get the child our unit’s customary gift for children
who have painful or scary procedures. Excited was an understatement to describe the patient
when I returned with a popsicle and our unit’s mascot pillow pet.
Once the procedure was completed the physician completed the discharge paperwork and
instructions. I happened to be the only staff nurse on the unit that day, so one of the managers
had come down to help me by managing all the discharges. The manager was in the room
completing the discharge when I heard a combination of laughter and tearfulness. The mother
was laughing because the child was upset because she had to leave; she wanted to stay and play
with me. I stopped what I was doing and went to comfort the child. I asked if I could have the
privilege of walking her to her car and she joyfully agreed. We walked with a slight skip, hand-
in-hand to her car; I helped buckle her in her car seat, and mom gave me a hug. I knew I had
connected with the child, but immediately went about my busy day without giving the encounter
another thought. Three weeks later the director of all of emergency services called me to his
office to tell me he had received a letter that he was forwarding to upper management as an
example of true nursing caring. The mother had written to explain and express appreciation that
not only had she perceived that her daughter was cared for, but she had been also. In her letter
she emphasized that her daughter attended the follow-up appointment with the pediatrician and
was relaxed and agreeable in a way the mother had never seen before. The mother attributed the
decreased fear and anxiety directly to the encounter she had had during her visit to our CEC and
the care she had received.

THEORY-BASED EXEMPLAR PAPER (TEP) FIRST DRAFT 8
Application of Theory to the Exemplar Encounter
The entire time for the presented exemplar was approximately an hour and half.
Knowing where to spend minutes with a scared child or family members allows for atraumatic
care to take place without the family feeling rushed while allowing nurses and physicians to
maintain a relatively appropriate pace. Reflecting on Watson’s Caritas Processes, some of the
specifics are highlighted events that demonstrate the application of the theory in my exemplar.
1. Practicing loving-kindness and equanimity
Being a member of a busy pediatric emergency room, exhibiting an authentic caring
presence from the first encounter is of upmost importance. Mindfully introducing myself with a
cheerful smile allows the family and patient to recognize that there is a purposeful connection
being made. Effort was made during this encounter to practice equanimity by taking the mother
and child to a safe, scare-free room and creating a peaceful environment by providing age
appropriate toys and a child-directed exam pace. It is my common practice to introduce the
providers and to reassure the patient and family that the provider is interested in giving the best,
atraumatic care possible. Noticing this child had extra fears, time was spent acknowledging the
child’s fears to promote a peace of mind that did result in reduced tears.
2. Being authentically present
Starting with mom and allowing her to express her story, I communicated to mom that
her child was important and to the child that I was safe. The child and I first connected with
Legos and toys during the initial exam. Allowing the child to play and not rushing allowed the
child to calm down at her pace. By taking an extra two to three minutes to sit with the child on
the bed while waiting for the physician allowed me to express that I was there for mom and
child.

THEORY-BASED EXEMPLAR PAPER (TEP) FIRST DRAFT 9
3. Cultivating one’s own spiritual practices, going beyond ego self
I have a Christian worldview that all humans are important and worthy of time and effort.
Though procedures and policies are set in place on how a facial laceration repair is to occur,
putting the patient first by allowing appropriate choices, listening to fears, and focusing without
immediately leaving the room gave me the freedom to be connected to my patient and her family
without worrying about all the tasks that were awaiting me once I exited the room.
4. Developing a helping-trusting, authentic caring relationship
During my interaction I worked to develop a helping-trusting relationship by truthfully
telling mother and patient the expectations of the pain management tools and the skill of the
doctor. Recognizing the mother’s guilt and fear, I took time to explain the procedures and CEC’s
atraumatic care policy. I purposely told the mother and patient about the doctor’s kindness and
that I trusted the doctor with my own child. Sitting with the child to play and allowing the child
into my personal space to play with Lego dolls that were on my badge reel were intentional acts
to allow the child to perceive my physical presence as safe.
5. Supporting the expression of positive and negative feelings
Both mom and child were allowed to express feelings of fear and anxiety without
condemnation. Mom was granted permission to feel guilty for an event she could not prevent
and then given reassurance that she did the right thing by bringing her child to a safe place to be
healed. At age four, shots are a common occurrence when a child goes to the doctor’s office; the
child’s fear of shots was not deemed irrational. Instead, the child was reassured this would not
happen and an alternative medication would be used.
6. Creatively using all ways of knowing as part of the caring process

THEORY-BASED EXEMPLAR PAPER (TEP) FIRST DRAFT 10
Even though mom and child had emotional and mental needs that were addressed through
the caring process, the main goal was to repair a facial laceration. The doctor present was one of
our most skilled and kindest physicians, but for some reason the child would not allow him to
touch her for the repair. He was unphased and together he and I used a work around solution.
Though I was not expecting to be so active in the repair, having a skill that allowed me to
quickly change roles was invaluable in this case.
7. Engaging in genuine teaching-learning experiences
In the discharge process, the mother was taught how to perform home care for the child’s
laceration repair. Mom was also given information on how to react when any future falls occur
and how to handle future injuries that will occur. Though the child undulated between tearful fits
and self-control, the child’s participation was applauded because she was working to do what she
could do at her age. Her behavior for allowing the staff to repair her laceration was positively
reinforced with a popsicle and a take home gift.
8. Creating healing environment
I utilized all the tools allotted to me for the care of this patient. Bringing toys into the
room, providing mom with a comfortable place to be during the procedure, utilizing a child life
specialist, and using atraumatic care techniques created a conducive healing environment.
9. Assisting with basic needs in all aspects of care
The child’s basic needs of fear and a laceration were met through listening, play, and
skillful repair. Mom’s fear and anxiety were addressed through discussion, comfort care, and
home care education.
10. Opening and attending to the mysterious; allowing and being open to miracles

THEORY-BASED EXEMPLAR PAPER (TEP) FIRST DRAFT 11
From my perspective the mysterious event was the deep connection I made within
minutes, to the point she would allow no one else to care for her. Though it is not uncommon for
children to want to stay at the CEC after a procedure to play, this child was refusing to go at all
because she wanted to play. The joy on her face when I offered to walk her to her car and our
final hug as I buckled her into her car will stay with me.
Conclusion
One of the tragedies of emergency care is that it is too easy for emergency room nurses to
be overwhelmed by the sheer volume of patients to be seen, to be shortsighted by tunnel-vision
for the numerous tasks that are required to achieve ER throughput, and to be intimidated by the
incessant administrative demands for daily productivity numbers that patient care is reduced to
seeing and treating the patient as a numerical chore rather than human being that is in search of
care for their perceived emergency (Johansen, 2014; Morgan, 2007; Weintraub, Hashemi, &
Kucewicz, 2006). When dealing with pediatric emergencies, there is an added dimension for the
nurse to be concerned with the parent or caregiver. In conducting a study based on Watson’s
Caring Theory Gillespie, Hounchell, Pettinichi, Mattei, & Rose found that there is usually a
discrepancy in the nursing care behaviors that are most important to the nurse and those which
are most important to the patient and the patient’s family (2012). Therefore, it is important to
recognize that though competency, knowledge and skill are important to the families of pediatric
patients, the nursing care that parents and families desire most is parental in nature, reflecting
attributes of affection, caring, watching, and protecting (Gillespie, Hounchell, Pettinichi, Mattei,
& Rose, 2012). Pediatric emergency care is chaotically fast paced, task oriented, and time
sensitive by nature. Utilizing caring behaviors as laid out by Jean Watson’s Human Caring

THEORY-BASED EXEMPLAR PAPER (TEP) FIRST DRAFT 12
Science make it possible to make deep authentic care connections even in time-constrained, task
oriented environment such as a pediatric emergency room.

THEORY-BASED EXEMPLAR PAPER (TEP) FIRST DRAFT 13
References
Byczkowski, T. L., PhD, Fitzgerald, M., PhD, Kennebeck, S., MD, Vaughn, L., PhD, Myers, K.,
MS, Kachelmeyer, A., BS, & Timm, N., MD. (2013). A comprehensive view of parental
satisfaction with pediatric emergency department visits. Annals of Emergency
Medicine, 62(4), 340-350. doi:10.1016/j.annemergmed.2013.04.025
Gillespie, G. L., Hounchell, M., Pettinichi, J., Mattei, J., & Rose, L. (2012). Caring in pediatric
emergency nursing. Research and Theory for Nursing Practice, 26(3), 216-232.
doi:10.1891/1541-6577.26.3.216
Johansen, M. L. (2014). Conflicting priorities: Emergency nurses perceived disconnect between
patient satisfaction and the delivery of quality patient care. Journal of Emergency
Nursing, 40(1), 13-19. doi:http://dx.doi.org.ezproxy.liberty.edu/10.1016/j.jen.2012.04.013
McEwen, M. & Wills, E. M. (2014). Theoretical basis for nursing (4th ed.). Philadelphia, PA:
Wolters Kluwer Health.
Morgan, R. (2007). Turning around the turn-arounds: Improving ED throughput processes.
Journal of Emergency Nursing, 33(6), 530-536. doi:10.1016/j.jen.2007.04.011
Peterson, C. (2010). ‘And I was very very crying’: Children's self-descriptions of distress as
predictors of recall. Applied Cognitive Psychology, 24(7), 909-924. doi:10.1002/acp.1636
Sitzman, K., & Watson, J. (2014). Caring science, mindful practice: Implementing watson's
human caring theory. New York, NY: Springer Publishing Company, LLC.
Wagner, A.L. (2010). “Core Concepts of Jean Watson’s Theory of Human Caring/Caring
Science.” Watson Caring Science Institute. Retrieved from
https://www.watsoncaringscience.org/files/PDF/watsons-theory-of-human-caring-core-
concepts-and-evolution-to-caritas-processes-handout.pdf

THEORY-BASED EXEMPLAR PAPER (TEP) FIRST DRAFT 14
Watson, J. (2008). Nursing: The philosophy and science of caring (Revised.). Boulder, Colo:
University Press of Colorado.
Watson, J. (2018). Caring Science Theory. Retrieved from https://www.watsoncaringscience.org
Weintraub, B., Hashemi, T., & Kucewicz, R. (2006). Creating an enhanced triage area improves
emergency department throughput. Journal of Emergency Nursing, 32(6), 502-505.
doi:10.1016/j.jen.2006.09.006
TEP PEER REVIEW FEEDBACK FORM
THEORY-BASED EXEMPLAR PAPER (TEP) FIRST DRAFT 15
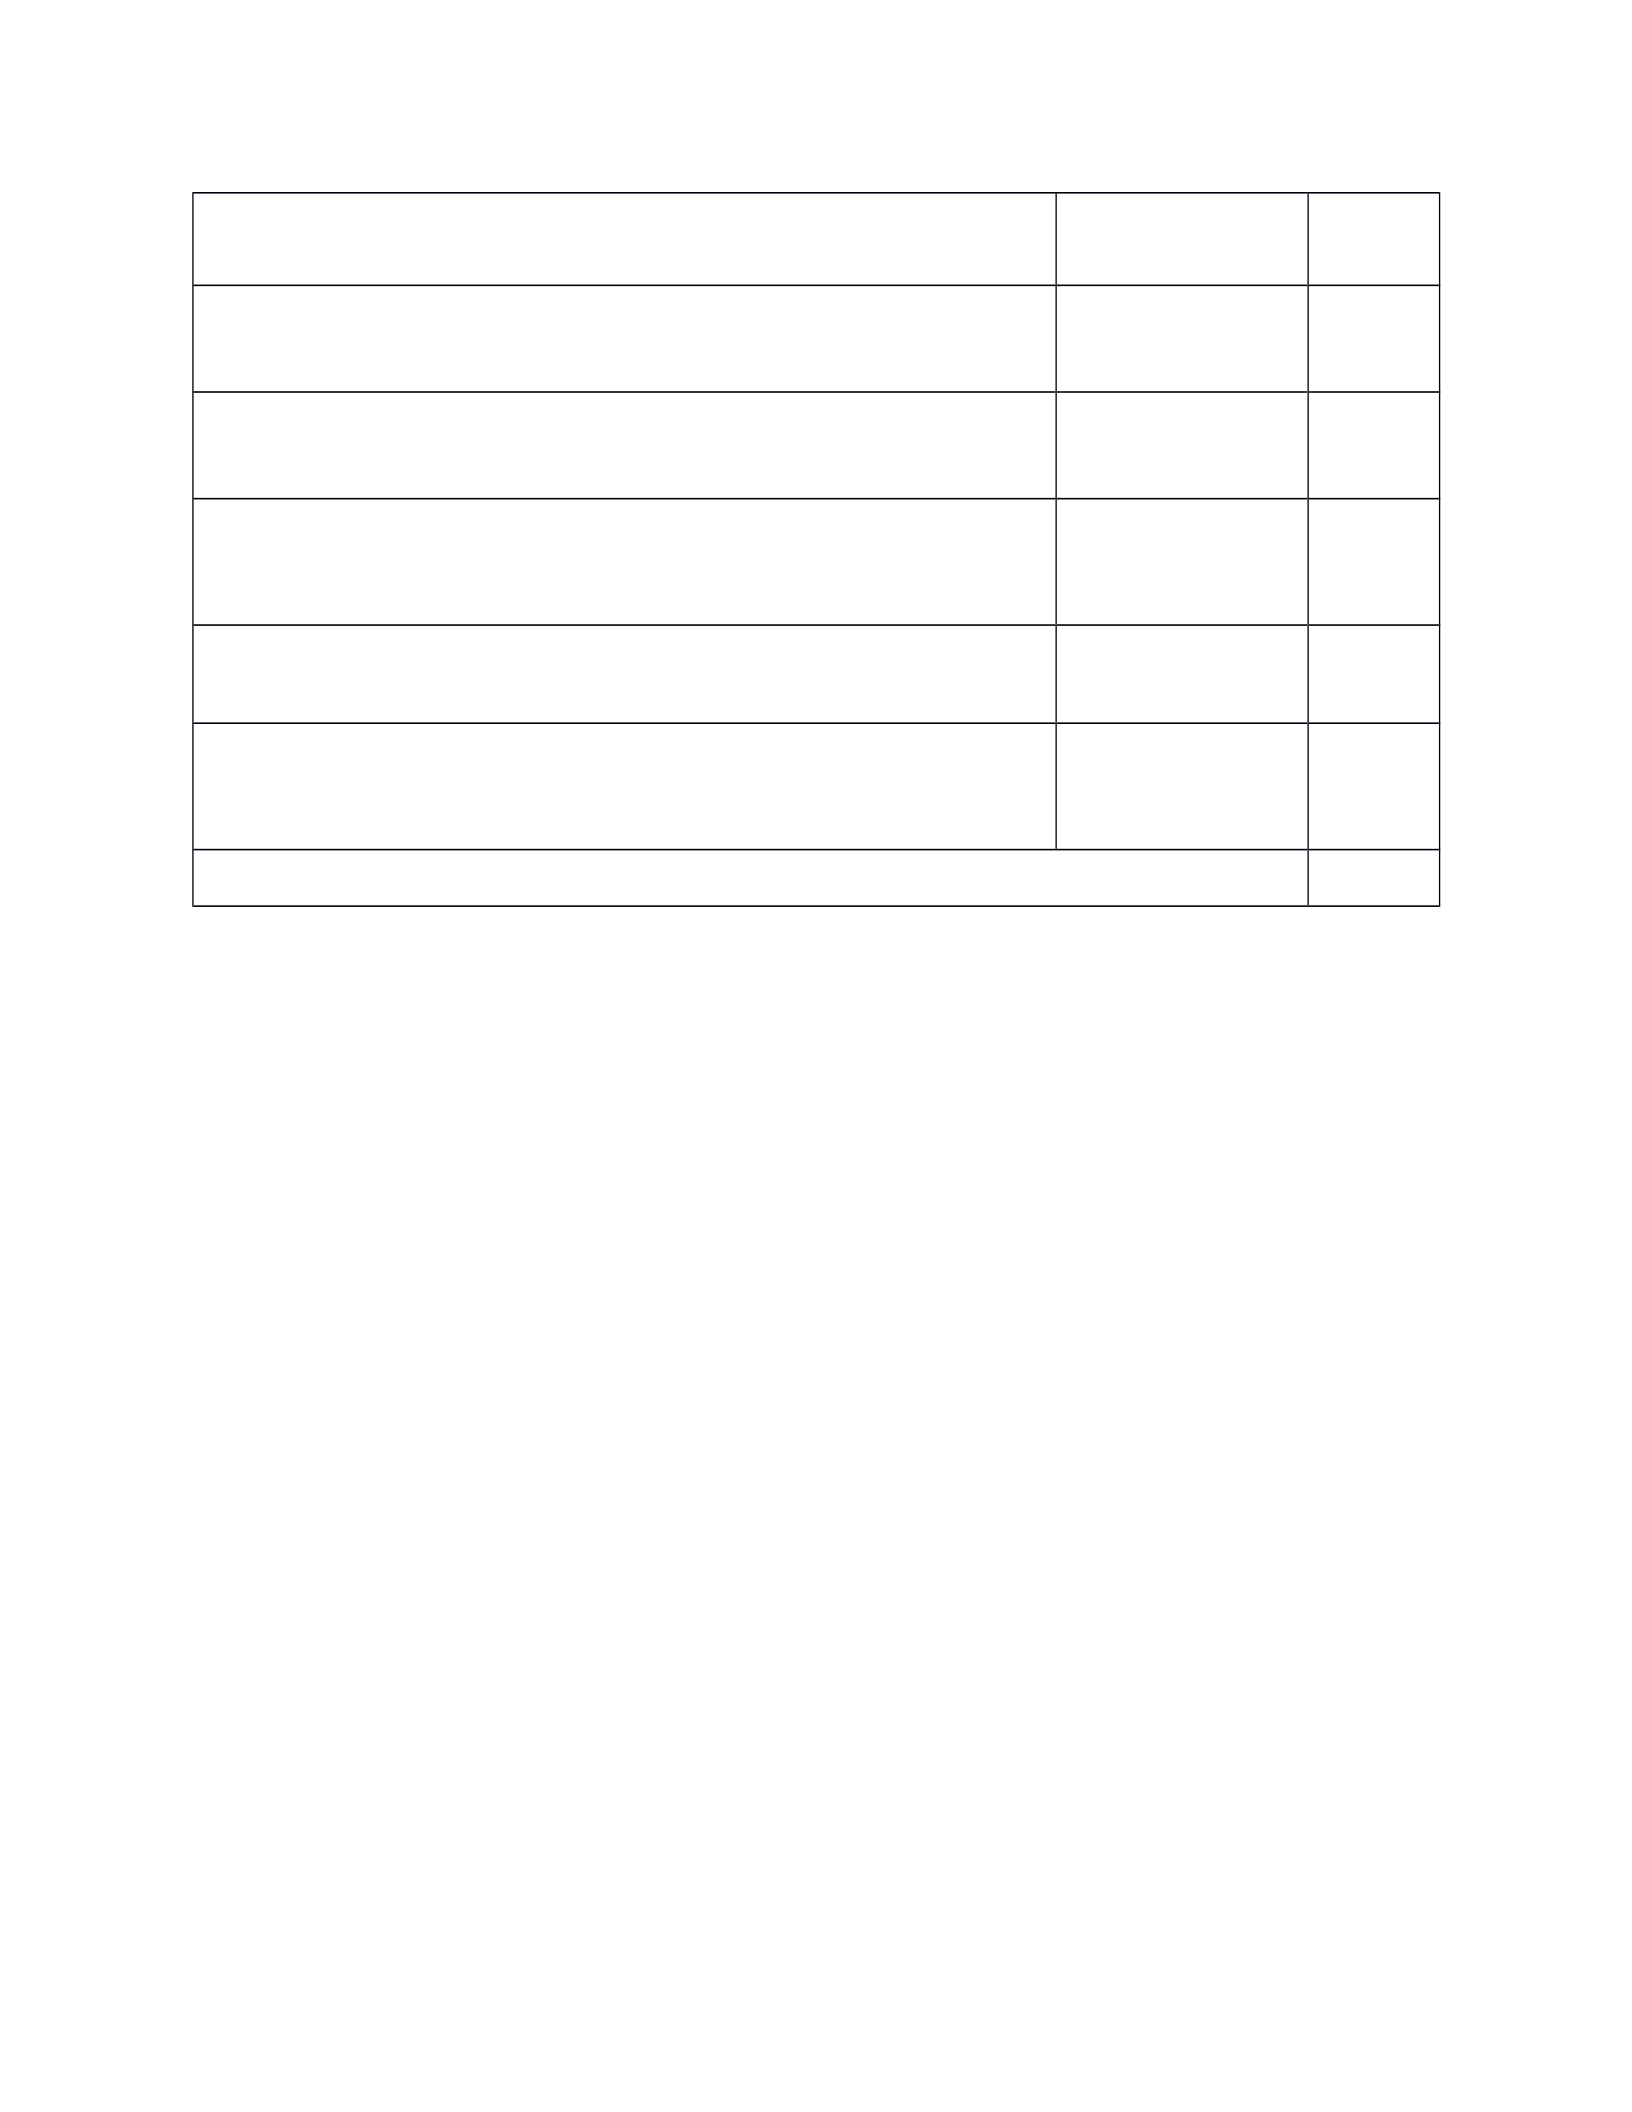
Criteria Points Possible
Points
Earned
Does the title accurately reflect the content of the paper? 0 to 5 points 3
Does the paper “flow” well? Is it easy and interesting to read? 0 to 15 points 15
Does the author make a good case for how the selected nursing theory
applies to practice (illustrated by exemplar and related discussion)?
0 to 30 points
30
Are sources in the paper accurately and adequately referenced? 0 to 10 points 10
How can the paper be improved? Include comments related to content,
grammar/spelling, and formatting.
0 to 15 points
13
Total 71/75
Summary of Comments/Peer’s Overall Impression:
The title of the paper utilized the standard title for the assigned task and did not
accurately reflect the content of the paper. Improvement is recommended on this aspect to
restructure the title in such a way that it will be reflective of the contents of the paper,
highlighting the exemplar and the nursing theory applied.
The paper is an interesting read with a good flow to it. I commend the good choice of the
exemplar and a thorough discussion of the theory’s application to the exemplar was noted. The
narration was interesting to read and spoke well on how important aspects of Watson’s theory
were applied to the clinical practice.
There is a good case for how the selected nursing theory applies to practice as illustrated
by the exemplar and related discussion. The paper utilized a very thorough approach in
highlighting all ten of Watson’s caritas processes and how they were applied in the exemplar
noted.

THEORY-BASED EXEMPLAR PAPER (TEP) FIRST DRAFT 16
The sources utilized in the paper are accurately and adequately referenced as per APA
guidelines. Most of the sources were current and were published in the past seven years, with
five cited sources that were published in the years 2006 to 2010.
There were minor grammatical errors noted throughout the paper. The formatting
correctly reflects APA guidelines and the content of the paper is presented in a clear, concise,
free-flowing manner significantly highlighting the chosen nursing theory.
Overall, the paper is excellent in terms of formatting and content, very good narration,
coherent thought process that is easy to comprehend and makes for a very interesting read.
Minor grammatical and spelling errors were noted but can easily be rectified. Only area of
improvement to note is to restructure the title to make it more reflective of the overall content of
the paper. Thank you for the opportunity to review your work, I learned a lot in terms of the
clinical application and will help me improve on my own work as well.

