



New graduate Registered Nurses and the Spectrum of Comfort in
Clinical Practice
This is the second article published from the data collected from the interviews with graduate
registered nurses in study 4. On revisiting the data, I identified a spectrum of comfort
considerations for graduate nurses and for the experienced nursing staff supporting them.
My contribution to the publication as corresponding author is detailed below. (An authorship
declaration is provided in Appendix 5).
Citation
Mellor, P.D. & Gregoric, C. (2019). New graduate registered nurses and the spectrum of comfort
in clinical practice. Journal of Continuing Education in Nursing, 50(12), 563-571.
[10.3928/00220124- 20191115-08]
Journal impact factor: 0.74 Citations: 1 (See Appendix 4 for details)
Authorship statement and publication background
This being the second article published from the original data obtained through interviews with
nine graduate nurses in study 4, there were minimal ethics requirements, apart from maintaining
confidentiality and integrity.
Research design: This article emerged from data obtained through interviews with nine graduate
nurses from rural and metropolitan areas, i.e., see publication 3 above: “Strategies new graduates
require to care and advocate for themselves”. There were a number of reasons for revisiting the data.
Detailed discussion of the methodology/methods has been provided in Chapter 1.
Data collection and analysis: As detailed previously for study 4, I engaged Lucy Atkinson
(research assistant and experienced interviewer) to undertake some of the interviews. I then
applied a renewed theoretical sensitivity and further synthesis. My analysis revealed the concept
of the “comfort zone” to be more complex than ordinarily considered. As a consequence, I drew up
a unique model illustrating the spectrum of comfort (Figure 1) and constructed the tables with an
underpinning theoretical framework. I also obtained feedback from Dr. Carolyn Gregoric (research
associate) and adjusted for readability and clarification. I reconstructed the informant
characteristics (Table 2) and selected the quotations representative of each theme. In addition, I
developed the reaction and response summary (Figure 2) and Spectrum of comfort:
considerations and support (Table 3).
Writing and editing: I was the corresponding author and wrote the initial draft for publication. This
included the passages selected for the purpose of illustrating each element of the ‘spectrum of
comfort’ in the results/discussion section. I also populated the ‘spectrum of comfort’ conceptual

model (Figure 1) and allocated characteristics appropriate to each concept in the theoretical
framework, i.e., neutral, positive, and negative regions of the comfort zone. My other
contributions included the design of figures/tables and manuscript revisions when responding to
the reviewers. Dr. Carolyn Gregoric as first co-author, offered feedback at each stage of
development, once again providing valuable perspective with regard to inclusions, conciseness,
and clarity. A complete version of this publication is included on the following pages.
New graduate registered nurses and the spectrum of comfort in
clinical practice
Abstract
The comfort zone is where a person consistently performs their role in an affective state devoid
of anxiety and as a rule without a feeling of risk. This study challenges the notion of a singular
“comfort zone” and suggests that a spectrum of comfort is a more accurate reflection of new
graduate experiences. A grounded theory methodology was used to identify and explain the
spectrum of comfort considerations helpful to nine new graduates amid their transition to
professional practice. Emerging from the data were themes which encompassed both the
positive and negative regions of the spectrum of comfort. Negative themes were: ‘feeling
abandoned’, ‘sometimes I get frightened’ and ‘feeling betrayed - catching hold’, while the more
positive themes were: ‘moderation of emotions’, and ‘letting go’. Each of these themes requires
an appropriate response from new graduates and experienced staff. The spectrum of comfort
model and practical considerations of support could accomplish this.
Throughout the first year of nursing practice, negative emotions or being “out of the comfort
zone” have been reported by new graduate registered nurses (NGRNs) in the literature. The
phrase being out of the comfort zone does not accurately reflect the range of comfort
experiences of new graduate RNs and therefore precludes individualised and targeted support.
This article challenges the notion of a singular comfort zone and suggests a spectrum of comfort
is a more accurate reflection of new graduates’ experience. There is a need to competently and
safely address the challenges experienced by new graduates during transition.
Background
NGRN’s report being out of their comfort zone for variable and extended amounts of time. On
certain days it is reported they are out of their comfort zone for short periods. On other days
they feel out of their comfort zone for most of the time (Duchscher, 2008). The expression of
‘being in one’s comfort zone’ is defined by White (2009) as having the following principle
elements:
The comfort zone is a behavioural state within which a person operates in an anxiety-
neutral condition, using a limited set of behaviours to deliver a steady level of
performance, usually without a sense of risk. (p.2)
In accordance with the previous definition, the comfort zone is typically described as a neutral region
of comfort, free of risk and challenge. Additionally, there is an array of positive and negative regions
of comfort described in the literature (Brown, 2008; White, 2009). The amalgamation of these three
regions of comfort is conceptualized as a spectrum of comfort in Figure 1.
Positive regions of comfort are characterized as the growth or learning zone, also called the
stretch zone or the optimal performance zone (Brown, 2008; White, 2009). The negative region
of comfort is experienced when an individual leaves the positive comfort region and moves into
the ‘panic zone’ or ‘danger zone’. In the negative region, feelings of being overwhelmed and
panic are often experienced and as a result performance suffers exponentially (Brown, 2008;
White, 2009). The neutral region where there is familiarity and little sense of risk is placed off–
center as White (2009) reflected that certain scenarios have the capacity to move individuals out
of the neutral region and into the negative region of the comfort spectrum more quickly than
others.
Table 1. Theoretical framework illustrating regions of comfort spectrum
Region of comfort Characteristics Expected performance
spectrum
Neutral Confident and happy; anxiety free; Acceptable
familiarity; predictable.
Positive
Stretching boundaries; risk; learning
and achievement; circle of safety Optimal
implicit.
Negative Fearful; stressed; overwhelmed; Compromised
unsupported.
Throughout the first year of nursing practice, negative emotions are often the norm, precipitated
primarily by being overwhelmed by unexpected responsibility (Pinchera, 2012). The effects of
these feelings of tension and resultant relief behaviors hinder social engagement and distort
interpretation of any informal feedback received from members of the inter-professional team
(Kim, Yeo, Park, Sin & Jones, 2018). These perceived or real threats to the psychological self

are purported to result in feelings of inadequacy and insecurity so severe they can cause the
NGRN to resist seeking help or avoid asking critical questions (Krozek, 2017). Other symptoms
can present such as physical or psychological illness, crying, acting out, withdrawal, irritation,
anger and avoidance (Washington, 2012). These extraordinary stressors place significant
demands on the NGRN’s resources of energy and ability to perform well in the context of
providing safe patient care. The phenomenon of “walking on thin ice” has been a description
used to depict this way of being for many NGRNs (Liang, Lin & Wu, 2018).
To address these concerns, increasing psychological capital can be beneficial (Kim & Yoo,
2018). In addition, observing successful role models, developing competency in nursing skills
(Walker & Campbell, 2013), accessing supportive mentors (Kim & Yoo, 2018) and continuing
exposure to the clinical environment have also been advocated. Successful overcoming of
obstacles is essential to NGRN’s psychological capital and the subsequent resilience that
ensues: “Studies have revealed that through the experience of a stressful event and
overcoming it through being resilient, individuals emerged stronger, perform better, and become
more confident and self-efficient” (Wahab, Mordiffi, Ang, & Lopez, 2017, p. 44).
Where resilience improves, reports of being in the negative region of the comfort zone
spectrum are reported to reduce. The interplay between self-talk, relationships with others and
the organizational culture influence the comfort zone perspective (Dwyer & Hunter Revell
2016). Camaraderie is considered an important factor to reducing stress in the health care
environment (Binte, Wahab, Mordiffi, Ang & Lopez, 2017). Camaraderie requires an attuned
social intelligence to effectively engage with others so that when experiencing panic NGRNs
are able to access an immediate circle of support (Walker & Campbell, 2013). These feelings
of insecurity are likely to continue until NGRNs are more settled into their environment and
have the requisite knowledge and skills to be more confident. Consequently, with improved
interpretation of relationships and a more positive lens through which they view themselves,
the new graduate begins to demand respect as a valued member of the team (Mansour &
Mattukoyya, 2018). The aim of this article is to explore the spectrum of comfort as a
determinant of success for NGRNs and recommend appropriate support to optimize learning
and performance.
Research Method
Grounded theory requires examination of the information collected and development of
new theoretical frameworks (Glaser & Strauss, 1967). However, where it is discovered

that a prior hypothesis fits the data with negligible distortion, verification or expansion of
the theory is a conceivable outcome (Glaser & Strauss, 1967; Strauss & Corbin, 1990).
Thoroughness of the investigation was achieved by utilizing the four criteria of Guba and Lincoln
(1989) - believability, transferability, dependability and confirmability. To provide believability,
predetermined closed questions were utilized to gather informant information and open-ended
inquiry was utilized to evoke richness of thought, emotion and strategies. Meetings were translated
verbatim. To help transferability, field notes were taken to supplement richness of the
information and provide context to the setting (Charmaz, 2014). An audit trail is accessible for
confirmability (Guba & Lincoln, 1989). Transferability is reflected in the rich depiction of the
context in which the nine informants were situated and their various transition experiences. To
provide reflexivity, interviews were shared between the investigator, who is a university
researcher, and an accomplished interviewer who was about to embrace her transition to
practice as a NGRN. The initial interview was undertaken with both investigators present so as
to contextualize the questions to be asked and to ensure confirmability (Guba & Lincoln, 1989).
Ethics endorsement was provided by the Southern Adelaide Clinical Human Research Ethics
committee, and site-explicit endorsement was obtained from all health units. Sources were
provided with a letter of introduction, an overview of the nature of the exploration and a
portrayal of expectations. Itemized questions were given to informants so consultation with
partners, colleagues, or family could occur prior to giving consent. Informants were likewise
educated that participation was voluntary, that they could cease participation at any time, and
could decline to answer any question.
A cursory view of the data from this research has been analyzed and reported previously.
However, the richness of data warranted further scrutiny. Since first publication deeper
analysis has revealed significant revelations with regard to new graduate nurses and the
spectrum of comfort in clinical practice. This separate examination utilizes grounded theory
method to investigate the spectrum of comfort experienced by NGRNs amid their progress
to proficient practice.
Data Collection
Nine NGRN informants volunteered to be involved from country and metropolitan South
Australia. Informants were individuals who had recently completed their transition-to-
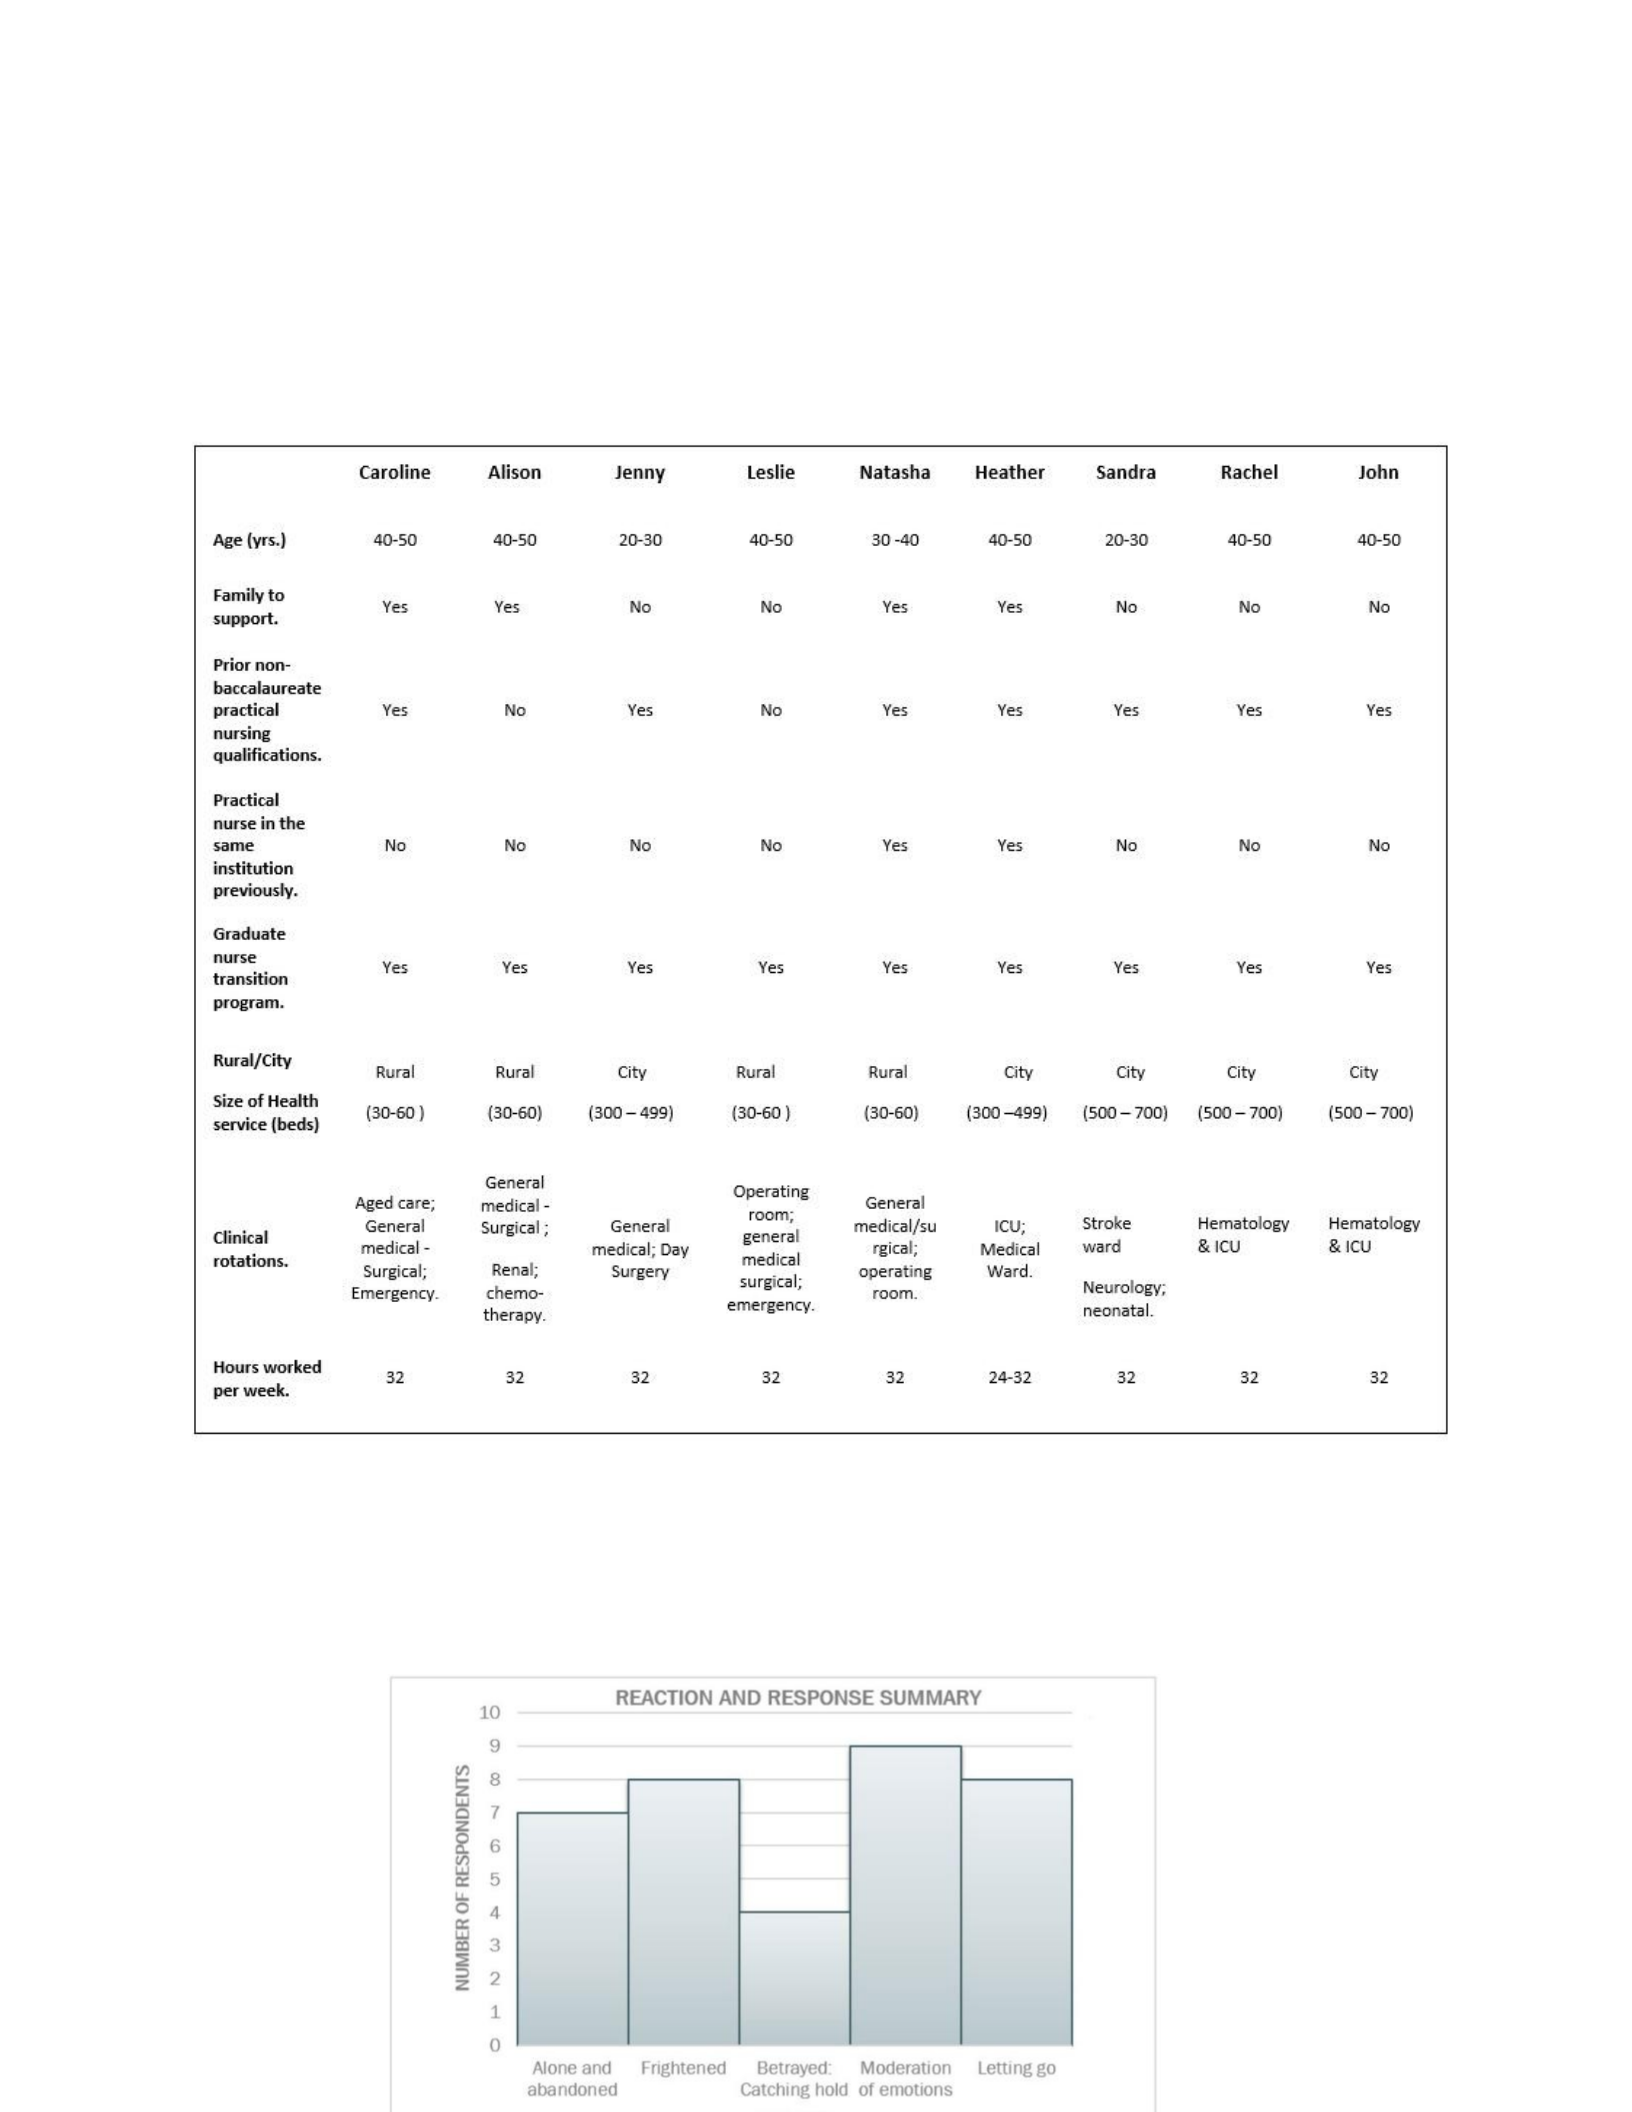
professional practice program. Table 2 provides a detailed record of every informant and their
background using pseudonyms for confidentiality.
Table 2. Informant characteristics
Findings
The results confirmed that NGRNs were challenged and that being in the negative region of the
spectrum of comfort was an overwhelming feature of their early practice (Figure 2).

Figure 2. Reaction & response summary (graphical representation)
Overall, the themes identified were both in the positive and negative and regions of comfort.
Negative themes were: ‘feeling abandoned’, ‘sometimes I get frightened’ and ‘feeling betrayed -
catching hold’, while the more positive themes were: ‘moderation of emotions’, and ‘letting go’.
Feeling alone and abandoned
Feelings of abandonment, a precursor to feeling frightened, were often reported and this
was expressed in a number of ways. For example:
I just felt like I had no one and I just felt very alone…What am I going to do? But I pulled
it together and I thought where else can I get help? So I was just brainstorming who can
I go to? What can I do? (Natasha)
I did feel really really stressed and knowing that I had all these other patients I had to go
to and I knew I couldn’t really ask anyone else to pick up my patients because they were
all in the same situation…may be another extra nurse with me, things would have been
different. (John)
There was nobody to call upon, which I did try and I wasn’t supported. (Alison)
Sometimes I get frightened:
As a consequence of abandonment, coping with the newness, routine and many expectations
of the RN role made NGRNs feel frightened. These ‘frightening’ feelings were expressed in
different ways. Some found it difficult to articulate how they felt as the emotions would virtually
rob them of their ability to speak. Others used descriptions that were emotive such as:
• It was really horrible.
• You do freak [out].
• [An] adrenaline feeling in my bones.
• Eyes were boggling.
• Mass confusion.

For example, Rachel was allocated to a patient who was on a noradrenaline infusion which she
was unfamiliar with. Rachel did not know how to titrate the dose and describes how stressed
she felt when left to this responsibility as a NGRN having not received any prior education and
support. She also made the decision to not be put in this situation again:
And it was frightening…it was like, do I put it up or do I put it down? I have no idea – it
was really horrible as I had no idea. (Rachel)
Similarly, Natasha was unable to address a serious problem with a patient because all of the
senior staff were busy with another emergency. She felt a range of powerful emotions
including anger at being left in this dilemma as a first year NGRN. However she was mostly
frightened at being abandoned:
I felt I suppose a range of emotions from anger to despair to almost breaking down
and having a big cry – what am I going to do? (Natasha)
In a further example, an NGRN identified as Sandra was asked to relieve in an unfamiliar ward
when her allocated ward did to not have many patients. She had been working with children
and the prospect of working with adults was frightening:
When I first got sent to an adult ward I freaked out…I got there and I just panicked.
They were like “Can you go and feed this man that’s had a stroke” and I'd never looked
after anyone that had had a stroke - I was petrified and I went into the bathroom and I
just cried and cried and cried, and I had a bit of a panic attack.
Feeling betrayed: Catching hold and not letting go
Graduates reported they were often left in situations for which they were not prepared and felt
betrayed, particularly when covertly allocated a patient who required care that was out of their
scope of practice. Due to having a negative experience on one occasion, the NGRN often made
a pact with themselves that this would not happen again. It became instinctive to catch hold of
the RN or staff member who was handing off and not end the conversation until satisfied that
their knowledge of the patient, equipment and care required was complete. In this example,
Rachel [all names are pseudonyms] demonstrates her concern at being left in charge of patients
for whom she was not prepared or informed of:
I won’t let the [hand-off] person go until they tell me [how to manage this patient] before
they leave and they won’t leave me in charge – I will not be left in charge of something that
I don’t know and are told ‘That’s okay, they’re fine you don’t need to do anything’.
In the following scenario a patient with chronic obstructive pulmonary disease was admitted to
the emergency department however the senior staff attributed anxiety as the underlying cause
of the symptoms being experienced. As a consequence, an unsuspecting Leslie (NGRN) was

assigned to this patient. Not only did she feel distressed and confused but had difficulty gaining
urgent assistance when the patient suddenly deteriorated:
He was just like staring with his eyes open, and the paramedic walked behind him and
shone his penlight in his eyes and said, ‘Oh they’re fixed and dilated’. So I went, ‘Oh holy
crap, what do I do’ – and it was just like this mass confusion. So the doctor was looking
right at me because I was in ED, so I called him over, and he didn’t realize that it was
urgent, so I called him over again, louder and I like clapped at him to try and make him
come. (Leslie)
Others ensured they had a back-up person to provide support when feeling overwhelmed by a
patient situation. In the following scenario, while questioning her own ability as a NGRN,
Caroline was still willing to respond to this cardiac emergency patient, providing that a support
person was nearby:
I have answered the ambulance radio and got the impression that I was going to be in
charge of this patient...and you just think… am I ready for this ?…am I able to respond
appropriately and all the rest of it ?…but you do have [support]...even if its administrative
support who are also nurses, you kind of…rush up to them and say...look I have got such
and such coming through can you just come and be nearby…so that if I am out of my
depth I can call on you… (Caroline).
Moderating emotions
Strategies NGRNs used to cope were primarily based around a change of mindset and
being proactive in whatever activity they were involved. A positive “mindset” and being
confident is a strategy specifically adopted by Caroline:
I do a lot of I think…positive mind…positive outcome sort of thing….a lot of you did well in
your studies you know a lot of stuff …you might not have the experience… but you know
you have the knowledge base and you should be able to draw upon that…try it and
reassure yourself that it is going to be OK. (Caroline)
Assuming full responsibility and being proactive to achieve safe patient outcomes was
also important to Heather:
So I need to do this, I need to do this…so you kind of like had a plan in your head of
what you needed to do and I think that kind of got me through. (Heather)
Natasha was able to use her emotional intelligence to restore her comfort into the positive
array. She was able to recognize her emotional state, interrupt her feelings of panic and adopt a
strategic approach and renewed mindset:
Just work off one thing at a time, one step, if you can't get to the last step that’s okay,
as long as you’ve done your important things then you're getting there. You’ve only
got so many hours in a day and you’ve got one pair of hands. (Natasha)

Letting go – restoration of positive equilibrium
Each graduate reflected on their progress and re-interpreted their experience and approach to
developing competence and confidence. As a consequence of these insights, they developed
resilience and assumed responsibility for their own performance and professional development.
Jenny doubted her recording of blood pressure readings which she described as “a bit low”
when the systolic reading was 85 mm Hg. After reflection, Jenny made the decision to not
always refer to others and to trust her own judgement:
So we had to call the MET team and so I think, now I think back about it, I could've
escalated it earlier, I could've been a bit more confident about it. So I guess in terms of
comfort zone, I probably shouldn't have needed to get the senior RN to check the blood
pressure, I could've just called the doctor straight away but it, I guess it comes with
experience. (Jenny)
Heather was initially fearful of the Intensive Care Unit however she turned the situation around:
I don’t know everything but I'm willing to learn and I'm willing to put the time and the
effort in so please feel free… I'm a sponge use me and abuse me. So they did and I
think that’s why I think I had such a positive first 6 months in ICU. (Heather)
Alison was keen to reduce unpredictability when caring for her patients. As a result, she made
the decision to restore equilibrium by being prepared as much as possible for any eventuality.
Her research and increased knowledge was empowering:
Like if I was not quite sure of this medical procedure … you could always go and look it
up and find a bit more information … doing a bit more studying… a bit more research
and knowledge is very empowering. (Alison)
Leslie made the decision to view the stress reaction to emergency situations as a
normal phenomenon:
I had a bad experience to start with, but then that primed me for the next time, which
was a much better experience and I was a lot more functional. I think it’s just exposure
to these things that helps …it’s always stressful and I think that’s quite a normal thing.
(Leslie)
Discussion
This study confirms that being in the neutral region of comfort was not a familiar experience for
NGRNs. As a novice member of the nursing profession the NGRN is uneasy in many different
contexts (Duchscher, 2008; Duchscher & Windey, 2018; Zheng, Lee & Bloomer, 2016). Most
were extremely driven to leave the negative region of the comfort spectrum after a short period
of time and were keen to restore a positive equilibrium as soon as possible (Herron, 2017). In

instances where incomplete information was provided many NGRNs felt betrayed and as a
consequence actively chose to take charge when there was a patient handoff i.e. where an
unfamiliar patient diagnosis, piece of equipment or procedure was encountered, the NGRN
would catch hold of the person doing the handoff and cling firmly onto this person, holding them
in virtual “custody”, until their fears were addressed. As a result, panic was reduced and the
NGRN able to function more effectively (Pinchera, 2012).
Graduates who were less assertive felt alone. They were reluctant to consult other staff whom
they perceived as too busy to help. The risk to patient safety and their own well-being was ever-
present (Ankers, 2018; Krozek, 2017 & Liang, Lin & Wu, 2018). At times they had to desist from
being overwhelmed and choose helpful thinking. Their emotional labor was at times draining but
most NGRNs actively moderated their emotions to overcome feelings of being overwhelmed
(Moran, 2012).
NGRN’s were able to proactively establish a positive equilibrium in a number of ways. This
included being proactive with their learning in anticipation of the likely patient situations to be
encountered (Binte, Wahab, Mordiffi, Ang & Lopez, 2017). Reframing can be performed by
adopting the the perspective that being fearful in a critical situation is a normal response. This
mindset enabled two NGRNs to view their inept response to an unfamiliar scenario as positive,
as the prior experience enabled them to perform competently, when confronted with the same
situation on a subsequent occasion (Binte, Wahab, Mordiffi, Ang & Lopez, 2017). Embracing
the perceived anxiety of being a novice in the intensive care unit environment ICU was
particularly helpful for one graduate, whereas other NGRNs’ reported that upon feeling anxious
or uncomfortable the strategy they instinctively used was to focus on talking openly with as
many people as possible. Being honest with their experiences and allowing space to reflect
and gain perspective was found to be beneficial in restoring a positive equilibrium. One new
graduate with well-developed social skills found that interacting with patients was a positive
way of relaxing when all around them were feeling uncomfortable (Walker & Campbell, 2013).
Experienced colleagues can do much to ameliorate the fear and uncertainty of the NGRN during
the first few months of practice. Planned oversight is an important consideration as proffered by
Ebright (2010, p.11) “What distribution of care delivery, or alternative assignment of RNs, would
assure that every patient was assessed by an experienced RN every shift?” It is essential that
purposeful support is provided, one that acknowledges the NGRN’s limited experience, affords
the necessary guidance and is sensitive to the need for support and a growing quest for

independence (Duchsher, 2008; Ebright, 2010; Gardiner & Sheen, 2017). There should also be
a culture of camaraderie (Binte, Wahab, Mordiffi, Ang & Lopez, 2017; Sedgwick & Pijl-Zeiber,
2015) and encouragement of NGRNs to seek help from experienced staff when feelings of
panic arise (Ebright, 2010). Table 3, summarizes the NGRN spectrum of comfort experience.
Each phase is accompanied by recommendations for self-support and support from
experienced staff:
Three negative regions were found within the spectrum of comfort - feeling alone, feeling
frightened and feeling betrayed. These reflect behavioral states that elicit a sense of risk and
anxiety in response to a trigger event. Rachel’s recount of panic after an incomplete handoff of a
critically ill new patient on a Noradrenaline infusion is an example of this. In these instances,
experienced staff need to watch-over the practice of the NGRN, verbally signal their availability
to
assist and ensure that handoff is complete. It is important to proactively ensure that all
appropriate
patient deterioration variables and MET considerations are included when handing off. With the
support of experienced staff, the NGRN should feel confident that they have a complete grasp
of
the situation and back up if required (Brown, Hochstetler, Rode, Abraham & Gillum, 2018;
Walton,
Lindsay, Hales & Rook, 2018).
The two positive regions within the spectrum of comfort, “moderation of emotions” and “letting
go”, reflect a behavioral state in which a change of mind-set by the NGRN avoids panic and
elicits a moderated response to the trigger event. This de-escalation allows the NGRN to assess
the patient situation effectively and safely. As the new graduate has exposure to the rigors of
their particular clinical environment, they become familiar with their personal and workplace
triggers and begin to develop a positive equilibrium in which they become more proactive with
learning new skills to reduce unpredictability. It is in these phases that staff can provide a
positive reassuring environment that is responsive to stress reactions and encourages personal
and professional development.
The neutral region of the spectrum of comfort is included in Table 3. It is a no growth zone,
performance is steady and there is little anxiety. Complacency can adversely affect patient safety.
Paradoxically this neutral region is routinely called the comfort zone, a zone in which most people

want to be all of the time. Being ‘out of the comfort zone’ is viewed as undesirable and this
perspective needs to be challenged.
Table 3. Spectrum of comfort: considerations & support
Limitation considerations
In this study nine NGRNs volunteered to be interviewed. Guest, Bunce and Johnson (2006) in
their study of interviews and qualitative analysis, found that themes and variability were usually
identified following only six interviews and saturation was anticipated after twelve interviews.
The original choice of data collection was to be face to face via interview; however, it became
necessary to interview some participants via telephone for convenience of the informants. In
order to not compromise the study with this variable, resources on effective telephone
interviews were accessed (Wilson, Roe & Wright, 1998) and as a consequence the richness of
data was preserved. Interviews took place throughout an eighteen month period because of

limited access to informants and access to venues with respect to ethics approval. It is unlikely
that the health cultures would change considerably throughout the extended interview period
however this is a possibility. The prior non-baccalaureate practical nursing history of many of
the respondents may influence the outcomes however it is usual for ENs (practical nurses) to
require the same level of support as other RN graduates and hence conceal their past
experience:
Surprisingly, GNs who had previously practiced as ENs (practical nurses) preferred not to
be identified as having previous nursing experience. This was because they feared being
treated by their nurse managers as already capable of practicing as RNs. In reality, this
group of new RNs needed support like any GN. (Cubit & Lopez, 2013 p. 210)
The age of the participants additionally needs consideration. Some informants were twenty to
thirty years of age, others were in their 50s. The average age of participants was thirty five
years. This demographic is consistent with the various studies reviewed (Cubit & Lopez, 2012)
however slightly higher than the average entry level of approximately 26.9 years in Australia
(Gaynor et al., p.16) and 30 years of age in the US (Allied Staffing Network, 2017) . The
average nursing workforce age is 44.4 years in Australia (AIHW 2015, p.1) and age 51 years in
the US (Allied Staffing Network 2017). Further detail of the life context in which informants were
functioning is provided in Table 2. The result of such multi-level influences was studied in detail
by Dwyer and Hunter Revell (2016, p. 113) and it was found that undergraduate preparation
was the most significant variable and “relatively few demographic variables consistently
influenced transitional outcomes”. In addition, all of the informants participated in a standardized
graduate program for government hospitals, which included orientation, preceptorship, and
clinical rotations. However, it is recognized that interpretation of the curriculum, organizational
culture, and resources available when implementing the graduate program could vary at
different locations (Table 2). Further research including systematic evaluation with control
groups of the interventions inherent in graduate programs is recommended in order to
determine their effectiveness.
Conclusion
This study challenges the notion of a singular “comfort zone” and suggests that a spectrum of
comfort is a more accurate reflection of NGRN experiences. A number of regions within the
spectrum have been identified. These regions are not linear but recursive as different situations
arise. The three negative regions on the spectrum include feeling abandoned; feeling frightened
and feeling betrayed. In response to the resultant panic and distress, more experienced

clinicians need to be aware of these reactions and respond effectively to ensure the emotional
well-being of the NGRN and provision of safe patient care. The positive regions within the
spectrum include taking charge through proactively seeking support and critical clinical
information, moderation of emotions and finally “letting go” as the NGRNs begin to change their
mindset and restore a positive equilibrium. Navigating the spectrum of comfort is a significant
challenge for NGRNs but with support they can succeed. These findings may assist NGRNs
and clinicians with further contextualizing the transition experience and nature of support
required by graduates.
References
Allied Staffing Network. (2017). America’s nurses are aging. Retrieved
from https://alliedstaffingnetwork.com/americas-nurses-are-aging/
Ankers, M.D., Barton C.A., & Parry, Y.K. (2018). A phenomenological exploration of graduate
nurse transition to practice within a transition to practice program. Collegian, 25, 319-325.
Australian Institute of Health and Welfare. (2015). Nursing and midwifery workforce 2015.
Retrieved from https://www.aihw.gov.au/reports/ workforce/nursing-and-midwifery-
workforce-2015/contents/who-are-nurses-and-midwives
Brown, J., Hochstetler, G.A., Rode, S.A., Abraham, S. P., & Gillum, D. R. (2018). The
lived experience of first year nurses at work. The Health Care Manager, 37(4), 281-289.
Brown M. (2008). Comfort zone: model or metaphor, Australian Journal of Outdoor
Education, 12(1), 3-12.
Charmaz K. (2014). Constructing grounded theory (2nd ed.). London: Sage.
Cubit, K., & Lopez, V. (2012). Qualitative study of Enrolled Nurses transition to Registered Nurses.
Journal of Advanced Nursing, 68 (1), 206-211.
Duchscher, J.B. (2008). A process of becoming: the stages of new nursing graduate
professional role transition. Journal of Continuing Education in Nursing, 39(10), 441– 450.
Duchscher J.E.B. (2009). Transition shock: the initial stage of role adaptation for newly
graduated Registered Nurses. Journal of Advanced Nursing, 65(5),

Duchscher, J., & Windey. M. (2018). Stages of transition and transition shock. Journal
of Continuing Education in Nursing, 34(4) 228 -232
Dwyer, P.A., Hunter Revell, S. M. (2016). Multilevel influences on new graduate nurse
transition.
Journal for Nurses in Professional Development., 32(3), 112.
Ebright, P. (2010). ‘The complex work of RNs: implications for healthy work environments,’ The
Online Journal of Issues in Nursing, 15. (1). http://nursingworld.org/MainMenuCategories/
ANAMarketplace/ANAPeriodicals/OJIN/TableofContents/Vol152010/No1Jan2010/Complex-
Work- of-RNs.html .
Gardiner, I & Sheen, J. (2017). Graduate nurses’ experience of feedback support and anxiety:
a pilot study. Australian Journal of Advanced Nursing, 35(1).
Glaser B. G. (1967). Basics of grounded theory analysis. USA: Sociology Press
CA.
Glaser B. G. (1967). The discovery of grounded theory: Strategies for qualitative research. New
York, USA: Aldine Publishing Company.
Herron, E.K. (2017). New graduate nurses’ preparation for recognition and prevention of failure
to rescue: A qualitative study, Journal of Clinical Nursing, 27, 390-401.
Liang, H., Lin, C., Wu, K. (2018). Breaking through the dilemma of whether to continue nursing:
Newly graduated nurses' experiences of work challenges, Nurse Education Today, 67, 72-76.
Kim, E.Y., Yeo J.H., Park, H., Sin, K. M., & Jones, C.B. (2018). Psychometric evaluation of the
environmental reality shock-related issues and concerns instrument for newly graduated
nurses. Nurse Education Today. 61, 106-111.
Krozek, C.F., (2017). Psychodynamics of onboarding new graduate nurses. The Journal
of Continuing Education in Nursing, 48(7), 299-301.
Kim, K.J., Yoo, M.S. (2018). The Influence of psychological capital and work engagement on
intention to remain of new graduate nurses. The Journal of Nursing Administration, 48(9),
459.

Mansour, M. & Mattukoyya, R. (2018). A cross-sectional survey of British newly graduated
nurses' experience of organization empowerment and of challenging unsafe practices. The
Journal of Continuing Education in Nursing, 49(10), 474-481.
Moran, R. (2012). Retention of new graduate nurses. Journal for Nurses in Staff
development, 6(28), 270-273.
Pinchera, B.J. (2012). Newly licensed nurses: A look at their first 18 months. Nursing, 42(5), 18.
Sedgwick, M., & Pijl-Zieber M. (2015). New rural acute care nurses speak up ‘‘we’re it’’ but
we’re not ready, Journal for Nurses in Professional Development, 31,(5) 278-283.
Strauss, A. L., & Corbin, J. (1990). Basics of qualitative research. California, USA:
Sage Publications.
Wahab, S.N.B.A., Mordiffi, S.Z., Ang, E., & Lopez, V. (2017). Light at the end of the tunnel:
New graduate nurses’ accounts of resilience: A qualitative study using Photovoice. Nurse
Education Today, 52, 43-49.
Walker, A., & Campbell, K. (2013). Work readiness of graduate nurses and the impact on job
satisfaction, work engagement and intention to remain, Nurse Education Today, 33 (12), 1490-
1495.
Walton, J., Lindsay, N., Hales, C., & Rook, H. (2018). Glimpses into the transition world:
New graduate nurses written reflections. Nurse Education Today, 60, 62-66.
Washington G. (2012). Performance anxiety in new graduate nurses. Dimensions of Critical
Care Nursing, 31(5), 295.
White, A. (2009). From comfort zone to performance management: Understanding development
to performance. White & Maclean Publishing, 1-20.
Wilson, K., Roe, B., & Wright L. (1998). Telephone or face-to-face interviews? A decision made
on the basis of a pilot study. International Journal of Nursing Studies, 35, 314 - 321.

Zheng, R., Lee, S.F., & Bloomer, M. J. (2016). How new graduate registered nurses
experience patient death: A systematic review and qualitative meta-analysis, International
Journal of Nursing Studies, 53, 320-330.

