



Cardiovascular Case Study- Seminar One
C. S. is a 42-year-old Hispanic male. He is married with four children, 10- year-old and 8-year-
old daughters and 7-year-old and 10 month old sons. He and his family moved to South
Carolina five years ago from Mexico.
Chief Complaint (CC):
"I need a refill on my sugar pills".
History of Present Illness (HPI):
C.S. is a 42-year-old Hispanic male who ran out of his metformin (Glucophage) for about a
month. He denies having a primary physician and states that since he doesn’t have any medical
insurance, so he usually goes to a free clinic for management of diabetes mellitus type 2.
Past Medical History (PMH):
Diabetes type 2 and obesity
Social History (SH):
C. S. works fulltime as a construction worker earning minimum wage and working six days a
week. Recently, with economic problems he has not been able to get full time hours and has
taken a second part time job as a landscaper working one or two days a week. He is the sole
financial provider for his family. He is married and has four children. He and his family moved to
South Carolina five years ago. C. S. denies tobacco use but does admit to binge drinking on the
weekends. He states drinking relieves his stress from work and finances.
Family History (FH):
Father- died two years ago at age 67-year-old from "heart problems" Mother- alive, 66-year-old
who has type 2 diabetes and hypertension
Current medications:
metformin (Glucophage) 500 mg po BID
Allergies:
denies any allergies to any medications or foods
C. S. arrives at the clinic to request a refill on his metformin (Glucophage).
1. What additional information does the nurse need to know?
● Diet, elimination patterns, activity-exercise program ( any chest pain or SOB during exercise), Sleep
habits, coping- stress tolerance patterns, and Value and belief patterns (cultural conflict)
● Vital signs, FSBS, inspection of skin, auscultation of heart and breath sounds. inspection/palpation of
neck.
Physical Assessment:
The nurse documents the following assessment findings:

General- obese Hispanic male in no acute distress. Calm, cooperative and pleasant. Ears, eyes,
nose, throat- within normal limits, without any significant findings. Neuro: AAOx3. PERRLA,
hearing intact bilaterally. Cardiovascular- chest symmetrical without any heaves. S1S2 without
any murmurs, rubs, or gallops. Point of maximal impulse (PMI) is at the 5th intercostal space, left
mid-clavicular line. +2 palpable bilateral radial and dorsalis pedis pulses. Respiratory: Lungs
clear to auscultation bilaterally with chest rise and fall symmetrical and unlabored. Skin- warm,
dry, and normal color for ethnicity. Abdomen- round, obese, soft, non-tender to palpation with
bowel sounds present in all quadrants. Last BM- this prior to arrival and reports stool is soft,
brown and formed.
When asked about his diet, C. S. states he eats breakfast and lunch at one of the fast food
restaurants closest to the construction site where he is working. His wife usually cooks ground
beef and enchiladas, tacos, burritos or tamales for dinner. He states he likes his foods spicy, hot
and usually fried and eats lots of cheese, sour cream, onions, and jalapeños with his foods. At
the end of the visit, the physician writes an order for a week supply of metformin (Glucophage)
and asks C. S. to return in one week. C. S. is instructed to fast for at least eight hours before his
next appointment.
2. Why does the physician want to see C. S. in one week for a follow up appointment?
● Possibly to allow the patient to be on the medication and see how the medication is managing his
diabetes.
● diagnosis of hypertension is based on the avg. of 2 or more properly measured seated BP readings on
each of 2 or more office visits. (pg. 741)
3. Discuss ethnic and cultural health disparities as it relates to C. S. and differentiate how this
compares to other ethnic and cultural groups. (Box on page 739)
● mexican americans have lower levels of awareness of hypertension and its treatments; are less likely to
receive treatment for hypertension; & have lower rates of adequate blood pressure control.
● african americans have the highest prevalence of hypertension, with women being higher than men.
Hypertension is more aggressive in African americans & results in more severe end organ damage. Do not
respond well to treatment with angiotensin inhibitors.
● African Americans and whites in the SOUTHEAST, have higher instances of Hypertension than similar
ethnic groups in other parts of the US.
4. Discuss the gender differences when the diagnosis of hypertension is given.
●MEN- before age 45, HTN is more common in men, men with HTN are more likely to suffer a MI
●Women- after age 64 HTN more common in women than men; partly due to menopause; more likely to
have a stroke; HTN occurs in 75% of African American women >75 years old. ACE INHIBiTOR- induced
cough & diuretic induced hyponatremia more common in women, HTN 2-3 times more common in
women on oral contraceptives (changes normally seen in the initial period of contraceptive use, during
dose changes and in Obese/Older women).
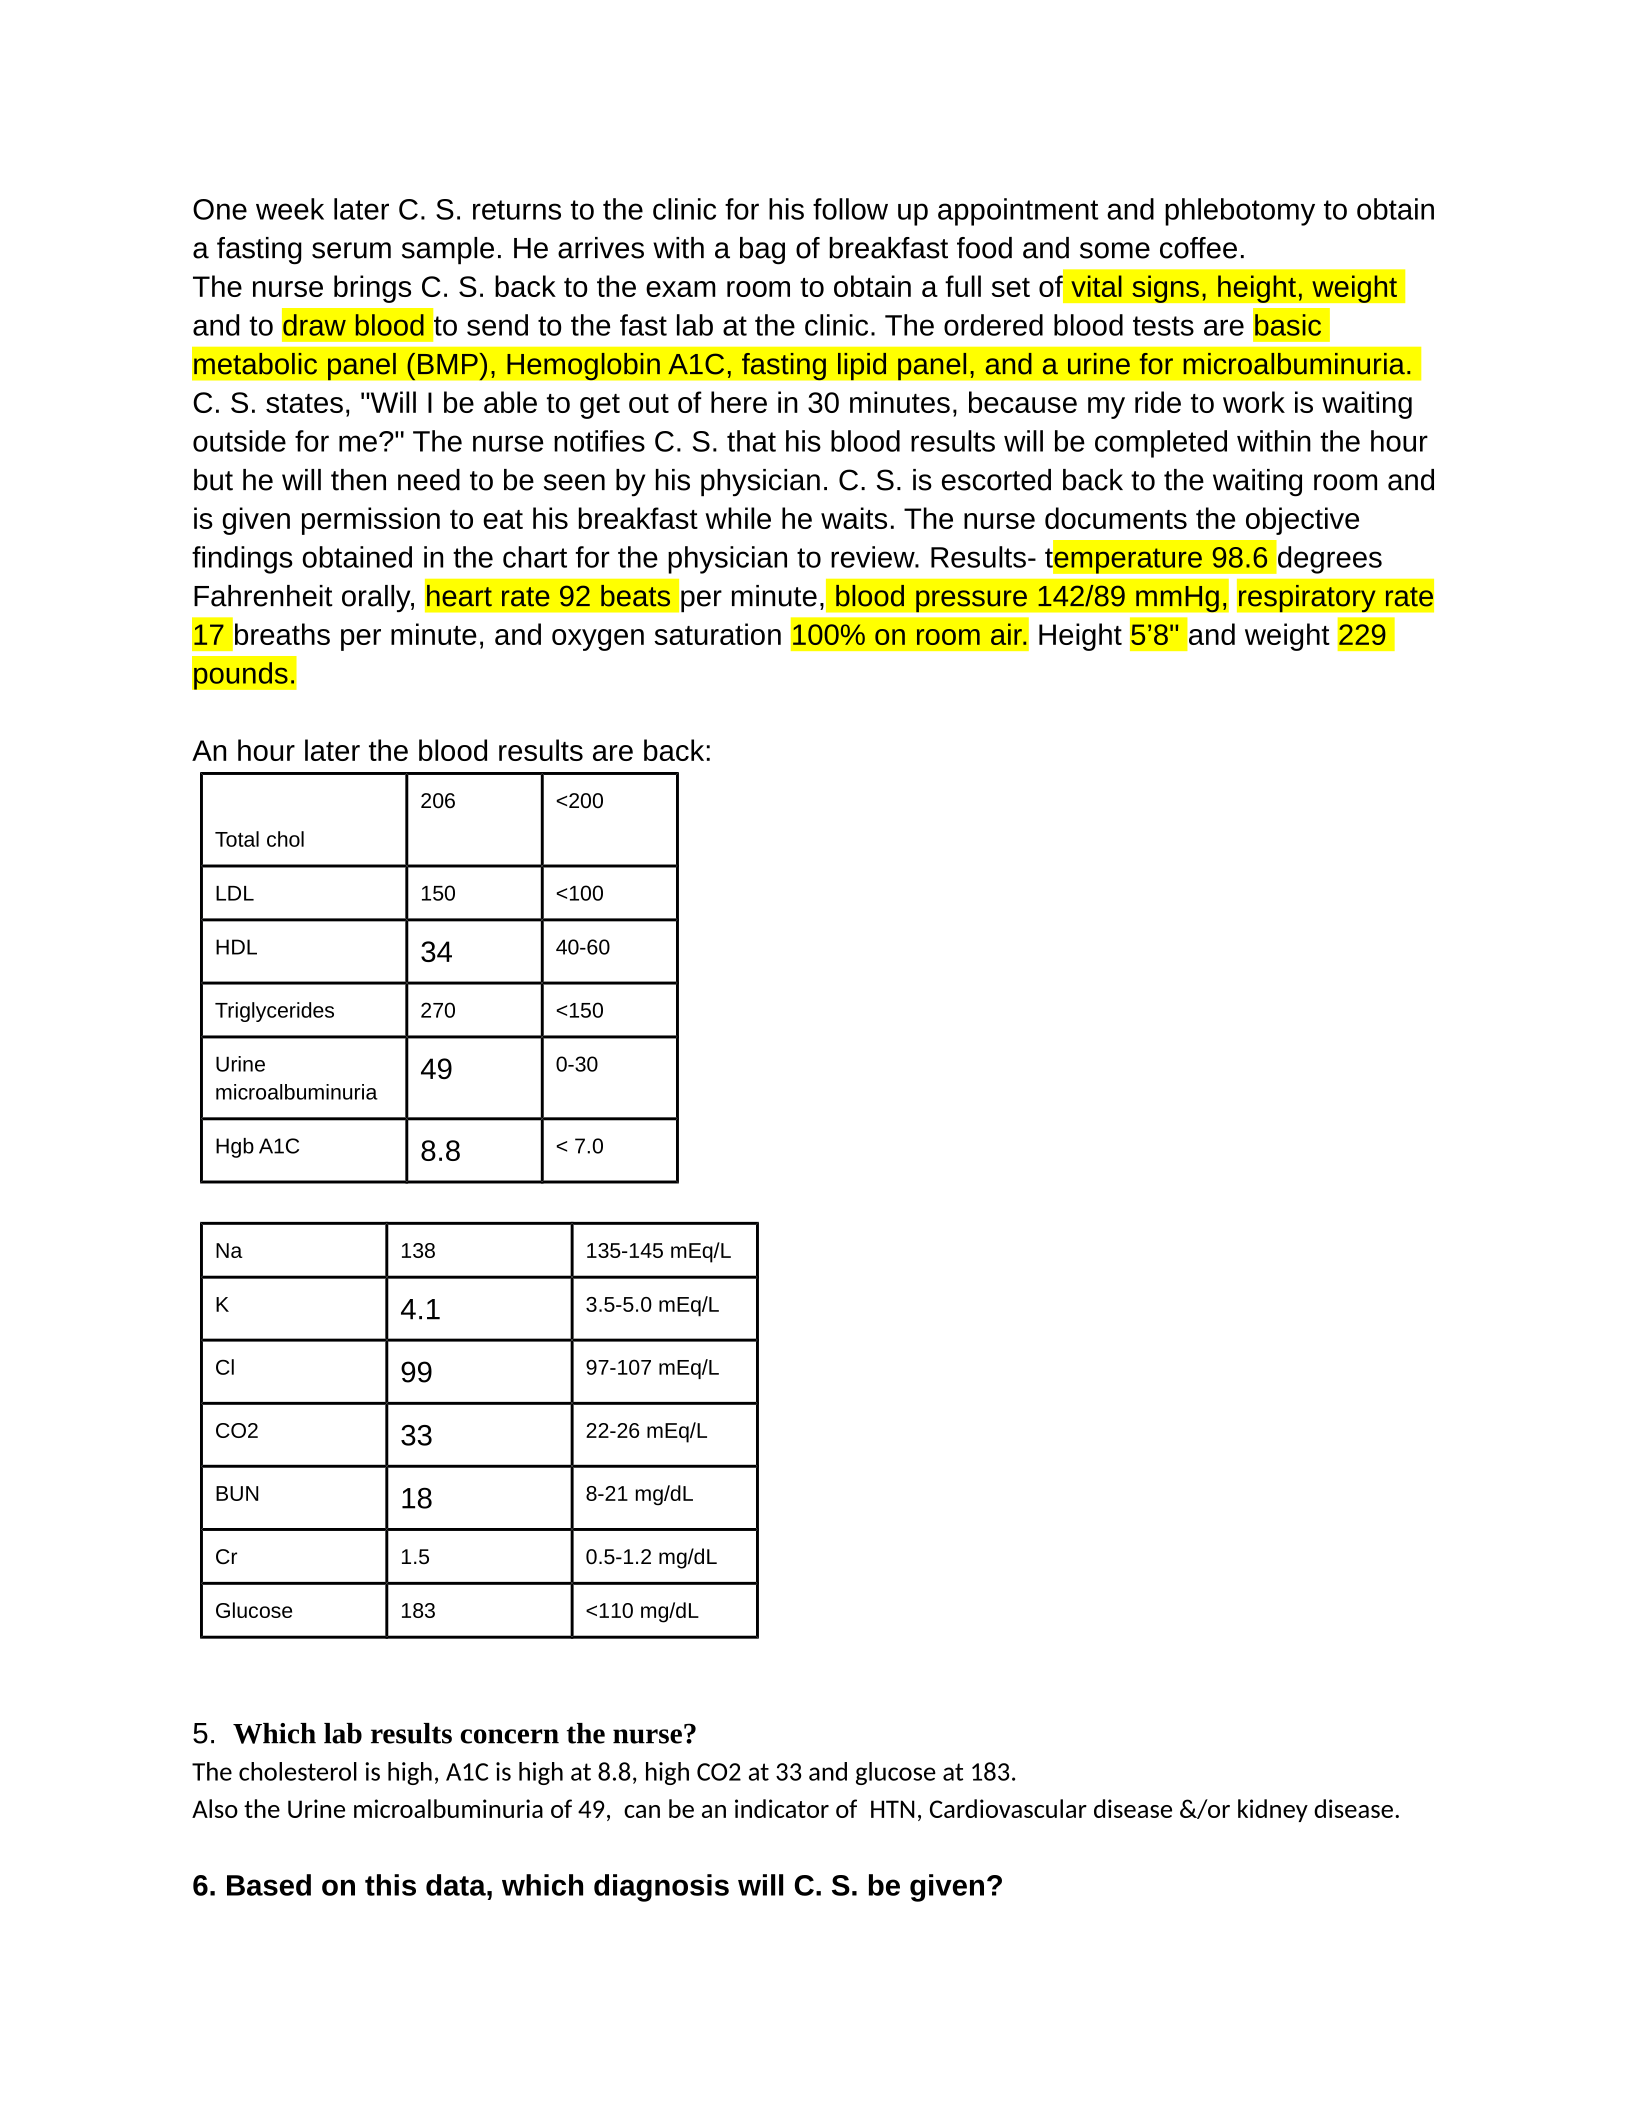
One week later C. S. returns to the clinic for his follow up appointment and phlebotomy to obtain
a fasting serum sample. He arrives with a bag of breakfast food and some coffee.
The nurse brings C. S. back to the exam room to obtain a full set of vital signs, height, weight
and to draw blood to send to the fast lab at the clinic. The ordered blood tests are basic
metabolic panel (BMP), Hemoglobin A1C, fasting lipid panel, and a urine for microalbuminuria.
C. S. states, "Will I be able to get out of here in 30 minutes, because my ride to work is waiting
outside for me?" The nurse notifies C. S. that his blood results will be completed within the hour
but he will then need to be seen by his physician. C. S. is escorted back to the waiting room and
is given permission to eat his breakfast while he waits. The nurse documents the objective
findings obtained in the chart for the physician to review. Results- temperature 98.6 degrees
Fahrenheit orally, heart rate 92 beats per minute, blood pressure 142/89 mmHg, respiratory rate
17 breaths per minute, and oxygen saturation 100% on room air. Height 5’8" and weight 229
pounds.
An hour later the blood results are back:
Total chol
206 <200
LDL 150 <100
HDL 34 40-60
Triglycerides 270 <150
Urine
microalbuminuria 49 0-30
Hgb A1C 8.8 < 7.0
Na 138 135-145 mEq/L
K4.1 3.5-5.0 mEq/L
Cl 99 97-107 mEq/L
CO2 33 22-26 mEq/L
BUN 18 8-21 mg/dL
Cr 1.5 0.5-1.2 mg/dL
Glucose 183 <110 mg/dL
5. Which lab results concern the nurse?
The cholesterol is high, A1C is high at 8.8, high CO2 at 33 and glucose at 183.
Also the Urine microalbuminuria of 49, can be an indicator of HTN, Cardiovascular disease &/or kidney disease.
6. Based on this data, which diagnosis will C. S. be given?

possible hypertension
7. Discuss the pathophysiology and clinical manifestations related to C. S. new diagnosis.
Hypertension increases the resistance against which the heart has to push causing the heart to
work harder. Untreated will cause target organ damage: myocardial infarction, cerebral vascular
accident, heart failure, renal disease and retinopathy.
Clinical manifestations:
silent killer, stroke, chronic high blood pressure, arteriosclerosis, heart attack or heart failure and
kidney failure
8. Identify at least five risk factors C. S. has that contributed to his diagnosis?
ETOH intake
Diabetes Mellitus
Elevated serum lipids (CAD)
socioeconomic status
stress
9. Discuss the complications related to this diagnosis.
Coronary Artery Disease (CAD)
Left Ventricular Hypertrophy
Heart Failure (HF)
Cerebrovascular disease (atherosclerosis)
Peripheral vascular disease
nephrosclerosis (hypertension is one of the leading causes of end stage renal failure)
retinal damage
10. What lifestyle modifications will the nurse teach C. S.? List five.
● Weight reduction- weight loss of 22 lbs can decrease SBP by 5-20 mm Hg
● Dietary sodium reduction or Dash Diet
● Moderation of alcohol consumption
● physical activity
● management of psychosocial risk factors
11. Discuss drug therapy options for C. S.
ACE inhibitors (Prils)
Alpha-Blockers (Zosins)
Angiotensin receptor blockers (Sartans)
Calcium Channel blockers (Pines w a few exceptions
Centrally acting agents (One to know)
Digoxin (Just Digoxin)
Diuretics ( Three types)

Nitrates (Nitroglycerin)
The physician writes a prescription for the following medications:
metformin (Glucophage) 1000 mg po BID losartan (Cozaar) 50 mg po once daily
12. Using the CWS medication list discuss the pharmacologic and therapeutic
classifications of losartan (Cozaar). What are the indications and actions of this drug?
List a life-threatening adverse reaction when taking this medication. List an adverse
reaction related to the endocrine system and related to fluid and electrolyte balance.
What will the nurse assess when a patient takes losartan? What teaching will the nurse
provide? What are the desired outcomes for this medication related to C. S.’s HTN and
DM?
● angiotensin ii receptor antagonists
● Indications
○ • Alone or with other agents in the management of hypertension.
○ • Treatment of diabetic nephropathy in patients with type 2 diabetes.
○ • Prevention of stroke in patients with hypertension and left ventricular
hypertrophy.
●Adverse Reactions/Side Effects
○CNS: dizziness, fatigue, headache, insomnia, weakness.
○CV: chest pain, edema, hypotension.
○EENT: nasal congestion.
○Endo: hypoglycemia, weight gain.
○GI: diarrhea, abdominal pain, dyspepsia, nausea.
○GU: impaired renal function.
○F and E: hyperkalemia.
○MS: back pain, myalgia.
○Misc: ANGIOEDEMA, fever.
■*CAPITALS indicates life-threatening.
■*italic indicates most frequent.
●Assessment
○• Assess BP (lying, sitting, standing) and pulse frequently during initial dose
adjustment and periodically during therapy. Notify health care professional of
significant changes.
○• Monitor frequency of prescription refills to determine compliance.
○• Assess patient for signs of angioedema (dyspnea, facial swelling). May
rarely cause angioedema.
●Lab Test Considerations
○• Monitor renal function. May cause ↑ BUN and serum creatinine.
○» May cause ↑ AST, ALT, and serum bilirubin.
○» May cause hyperkalemia.
○» May cause slight ↓ hemoglobin and hematocrit.

●Patient/Family Teaching
○• Emphasize the importance of continuing to take as directed, even if feeling well.
Take missed doses as soon as remembered if not almost time for next dose; do
not double doses. Medication controls but does not cure hypertension. Instruct
patient to take medication at the same time each day. Warn patient not to
discontinue therapy unless directed by health care professional.
○• Caution patient to avoid salt substitutes containing potassium or foods
containing high levels of potassium or sodium unless directed by health care
professional. SeeFood Sources for Specific Nutrients.
○• Caution patient to avoid sudden changes in position to decrease orthostatic
hypotension. Use of alcohol, standing for long periods, exercising, and hot
weather may increase orthostatic hypotension.
○• May cause dizziness. Caution patient to avoid driving or other activities
requiring alertness until response to medication is known.
○• Advise patient to notify health care professional of all Rx or OTC medications,
vitamins, or herbal products being taken and to consult with health care
professional before taking other medications.
○• Instruct patient to notify health care professional of medication regimen before
treatment or surgery.
○• Instruct patient to notify health care professional if swelling of face, eyes,
lips, or tongue or if difficulty swallowing or breathing occur.
○• Advise women of childbearing age to use contraception and notify health care
professional if pregnancy is planned or suspected, or if breastfeeding. Losartan
should be discontinued as soon as possible when pregnancy is detected.
○• Emphasize the importance of follow-up exams to evaluate effectiveness of
medication.
○• Hypertension: Encourage patient to comply with additional interventions for
hypertension (weight reduction, low-sodium diet, discontinuation of smoking,
moderation of alcohol consumption, regular exercise, stress management).
Medication controls but does not cure hypertension.
○» Instruct patient and family on proper technique for monitoring BP. Advise them
to check BP at least weekly and to report significant changes.
●Evaluation/Desired Outcomes
○• Decrease in BP without appearance of excessive side effects.
○• Delayed progression of diabetic nephropathy in patients with type 2 diabetes.
○• Decreased incidence of stroke in patients with hypertension and left ventricular
hypertrophy.
13. Using the nursing process develop one nursing diagnosis.
● ineffective self-health management r/t lack of knowledge of pathology,
complications, & management of hypertension.
14. Discuss the patient teaching related to this new diagnosis?

refer to page 755 table 33-14
15. On your own, research the following evidence-based practice websites that provide
guidelines for the management and treatment of C. S. diagnosis.
Seventh report of the Joint National Committee on Prevention, Detection, Evaluation, and Treatment of
High Blood Pressure (JNC-7);
US Department of Health and Human Services:
Healthy People 2010; and the National Heart, Lung, and Blood Institute: Your guide to lowering your
blood pressure with DASH, NIH.
Powered by TCPDF (www.tcpdf.org)

