


1
DETERMINANTS OF CLIENT SATISFACTION WITH
OUTPATIENT HEALTHCARE SERVICES AT BUSIA DISTRICT
HOSPITAL, KENYA
Patient satisfaction is a key criterion by which the quality of health care services is
evaluated (Young et al., 2000). It can be defined as a state of pleasure or contentment
with an action, event or service, especially one that was previously desired (Hornsby
and Crouther, 2000). In medical care, patient satisfaction can be considered in the
context of patients’ appraisal of their desires and expectations of health care.
Patient satisfaction data are routinely collected and used for continuous quality
improvement by health care institutions and hospitals (Donabedian, 1988, and Cleary
and McNeil, 1988). According to Otani et al. (2005), there are several motivations for
surveying patient satisfaction. It may influence health care utilization, can be a
predictor of subsequent health-related behavior and whether patients are willing or
not to recommend their health care provider to others. Patient satisfaction is
measured over a wide range of healthcare service dimensions, including availability,
accessibility and convenience of services, technical competence of providers,
interpersonal skills and the physical environment where services are delivered
(Grogan et al., 2000). A number of studies on patient satisfaction with healthcare
services have reported high levels of patient satisfaction (Schoenfelder et al., 2011

2
and Meredith et al., 2008). Other studies have, however, reported low levels of patient
satisfaction with healthcare services (Sekandi et al., 2011). However, it remains
controversial whether patients’ ratings reflect anything about technical quality or
simply the interpersonal skills of the healthcare service provider (Pascoe, 1983).
Various studies have shown diverse factors that are thought to influence the level of
patient satisfaction. A study in Germany identified ten determinants of patient
satisfaction to be: outcome of treatment, kindness of hospital nurses and physicians,
organization of procedures and operations, quality of food, accommodation,
individualized medical care, discharge procedures and instructions, physicians’
competence and cleanliness (Schoenfelder et al., 2011). Other studies have shown that
patients’ perceptions of quality are often influenced by their interaction with the
healthcare provider; the thoroughness with which the providers examine and
communicate with their patients (Meredith et al., 2008, and Marcinowiz et al., 2009).
This therefore shows that the determinants of patient satisfaction varies from one
setting to another and the key determinants should be altered in order to improve
patient satisfaction with quality of health care services.
Kols and Sherman (1998) observed that for health services to satisfy patients’ needs,
health care systems need to undergo continuous transformation in accordance to
priority needs of clients. This can only be achieved by continuously determining these
needs through patient’s satisfaction surveys to ensure quality health care services.
In Kenya, one of the aims of the Ministry of Medical Services’ Strategic Plan 2008-
2012 is to ensure that public hospitals provide appropriate, high quality medical
services to meet the 21st century medical care needs of Kenyans. The ministry plans to

3
achieve this by improving efficiency in the management and delivery of medical
services in public hospitals. The ministry also aims to improve quality of hospital
services by at least 50% as measured technically, and by clients, and also seeks to
understand patient and institution characteristics that determine satisfaction with care
(MOMS, Strategic Plan 2008-2012). There are few published studies on patient
satisfaction or perceptions of quality with services that are delivered in Kenyan public
or private hospitals, and the practice of assessing patient satisfaction is rare. At Busia
District Hospital, the proposed Busia County referral hospital, there is no routine
system for assessing patient satisfaction. Preliminary reports from the hospital’s social
worker reveals patients’ dissatisfaction with the services offered. The outpatient
department (OPD) is the first point of contact with a patient and serves as the window
to any healthcare services provided to the community. The care in OPD indicates the
quality of services of a hospital and is reflected by patients’ satisfaction and their
perception about the services.
A visit to Busia District Hospital reveals a number of issues that need to be addressed.
According to the facility’s social worker, preliminary reports indicate patients’
dissatisfaction with healthcare services. Moreover, with the introduction of the civil
servants’ outpatient National Hospital Insurance (N.H.I.F.) scheme, preliminary
reports indicate that a significant number of civil servants working in the district
prefer private health facilities over Busia District Hospital. This is despite the fact that
Busia District Hospital boasts of a significant number of medica l specialists. At Busia
District Hospital, there is no routine system for assessing patient satisfaction with
health care services. This is one of the largest level 4 hospitals in Kenya and it is the

4
proposed Busia County referral hospital. It is important to ensure that high quality
healthcare services, responsive to patients’ needs, are provided in this facility.
Statement of the Problem
Patient satisfaction data are routinely collected and used for continuous quality
improvement by health care institutions and hospitals in developed countries.
Globally, a critical aspect in the patient satisfaction’s measurement is that models and
instruments sometimes reflect the providers’ perspective rather than the patients’
one.While this is gaining momentum in a number of developing countries especially
in Asia, the practice is, however uncommon in African settings. In this respect a
population satisfaction level of 50% was assumed since there were no prior published
studies on outpatient satisfaction in Busia or any other similar setting in Kenya.. In
order for Busia district hospital to ensure that high quality healthcare services,
responsive to patients’ needs, are provided in the facility, there is need for continuous
evaluation of these services. Preliminary reports indicated patients’ dissatisfaction
with healthcare services at the Busia District Hospital (BDH), with no routine system
in place for patients to assess the perceived quality of these services. Lack of adequate
healthcare resources, understaffing and poor working conditions of healthcare
workers are thought to compromise the quality of care given to patients at Busia
District Hospital. Other factors include management related challenges occasioned by
devolution of the healthcare docket in Kenya. The researcher therefore set out to
undertake a study with the aim of determining the levels and determinants of patients’
satisfaction with healthcare services in outpatient clinics at Busia District Hospital.
The outcome of this research would serve as a basis for management to ensuring cost
effective, efficient and quality health care services are offered at the hospital and it

5
would be a significant step in the direction of evidence based health care service
practice.
Study Justification
The aim of this study was to provide information which would form a link of
understanding between the hospital management and the clients based on the latter’s
experience and perceptions of the health care services. Hence, its outcome would
serve as a basis for management to ensuring cost effective, efficient and q uality health
care services are offered at the hospital. The researcher felt that the outcome of the
study would be a significant step in the direction of evidence based health care service
practice.
1.1. Study Objectives
1.1.1. Main Objective
To assess the determinants of patients’ satisfaction with health-care services in
outpatient clinics at Busia District Hospital
1.1.2. Specific Objectives
1. To assess the perceived importance of healthcare service attributes.
2. To determine the general level of patient satisfaction with outpatient
healthcare services at Busia District Hospital, Kenya.
3. To identify the factors associated with the level of patient satisfaction with
outpatient healthcare services at Busia District Hospital, Kenya.

6
4. To determine the relationship between factors associated with patient
satisfaction and levels of patients’ satisfaction with outpatient healthcare
services at Busia District Hospital.
1.2. Research Questions
1. What is the perceived importance of healthcare service attributes?
2. What is the general level of patient satisfaction with outpatient healthcare
services at Busia District Hospital?
3. What factors are associated with the level of patient satisfaction with
outpatient healthcare services at Busia District Hospital?
4. What is the relationship between factors associated with patient satisfaction
and the levels of patients’ satisfaction with outpatient healthcare services at
Busia District Hospital?
1.3. Assumption of the Study
That the respondents would provide accurate and truthful information based on
services offered at the facility.

7
1.4. Conceptual Frame work
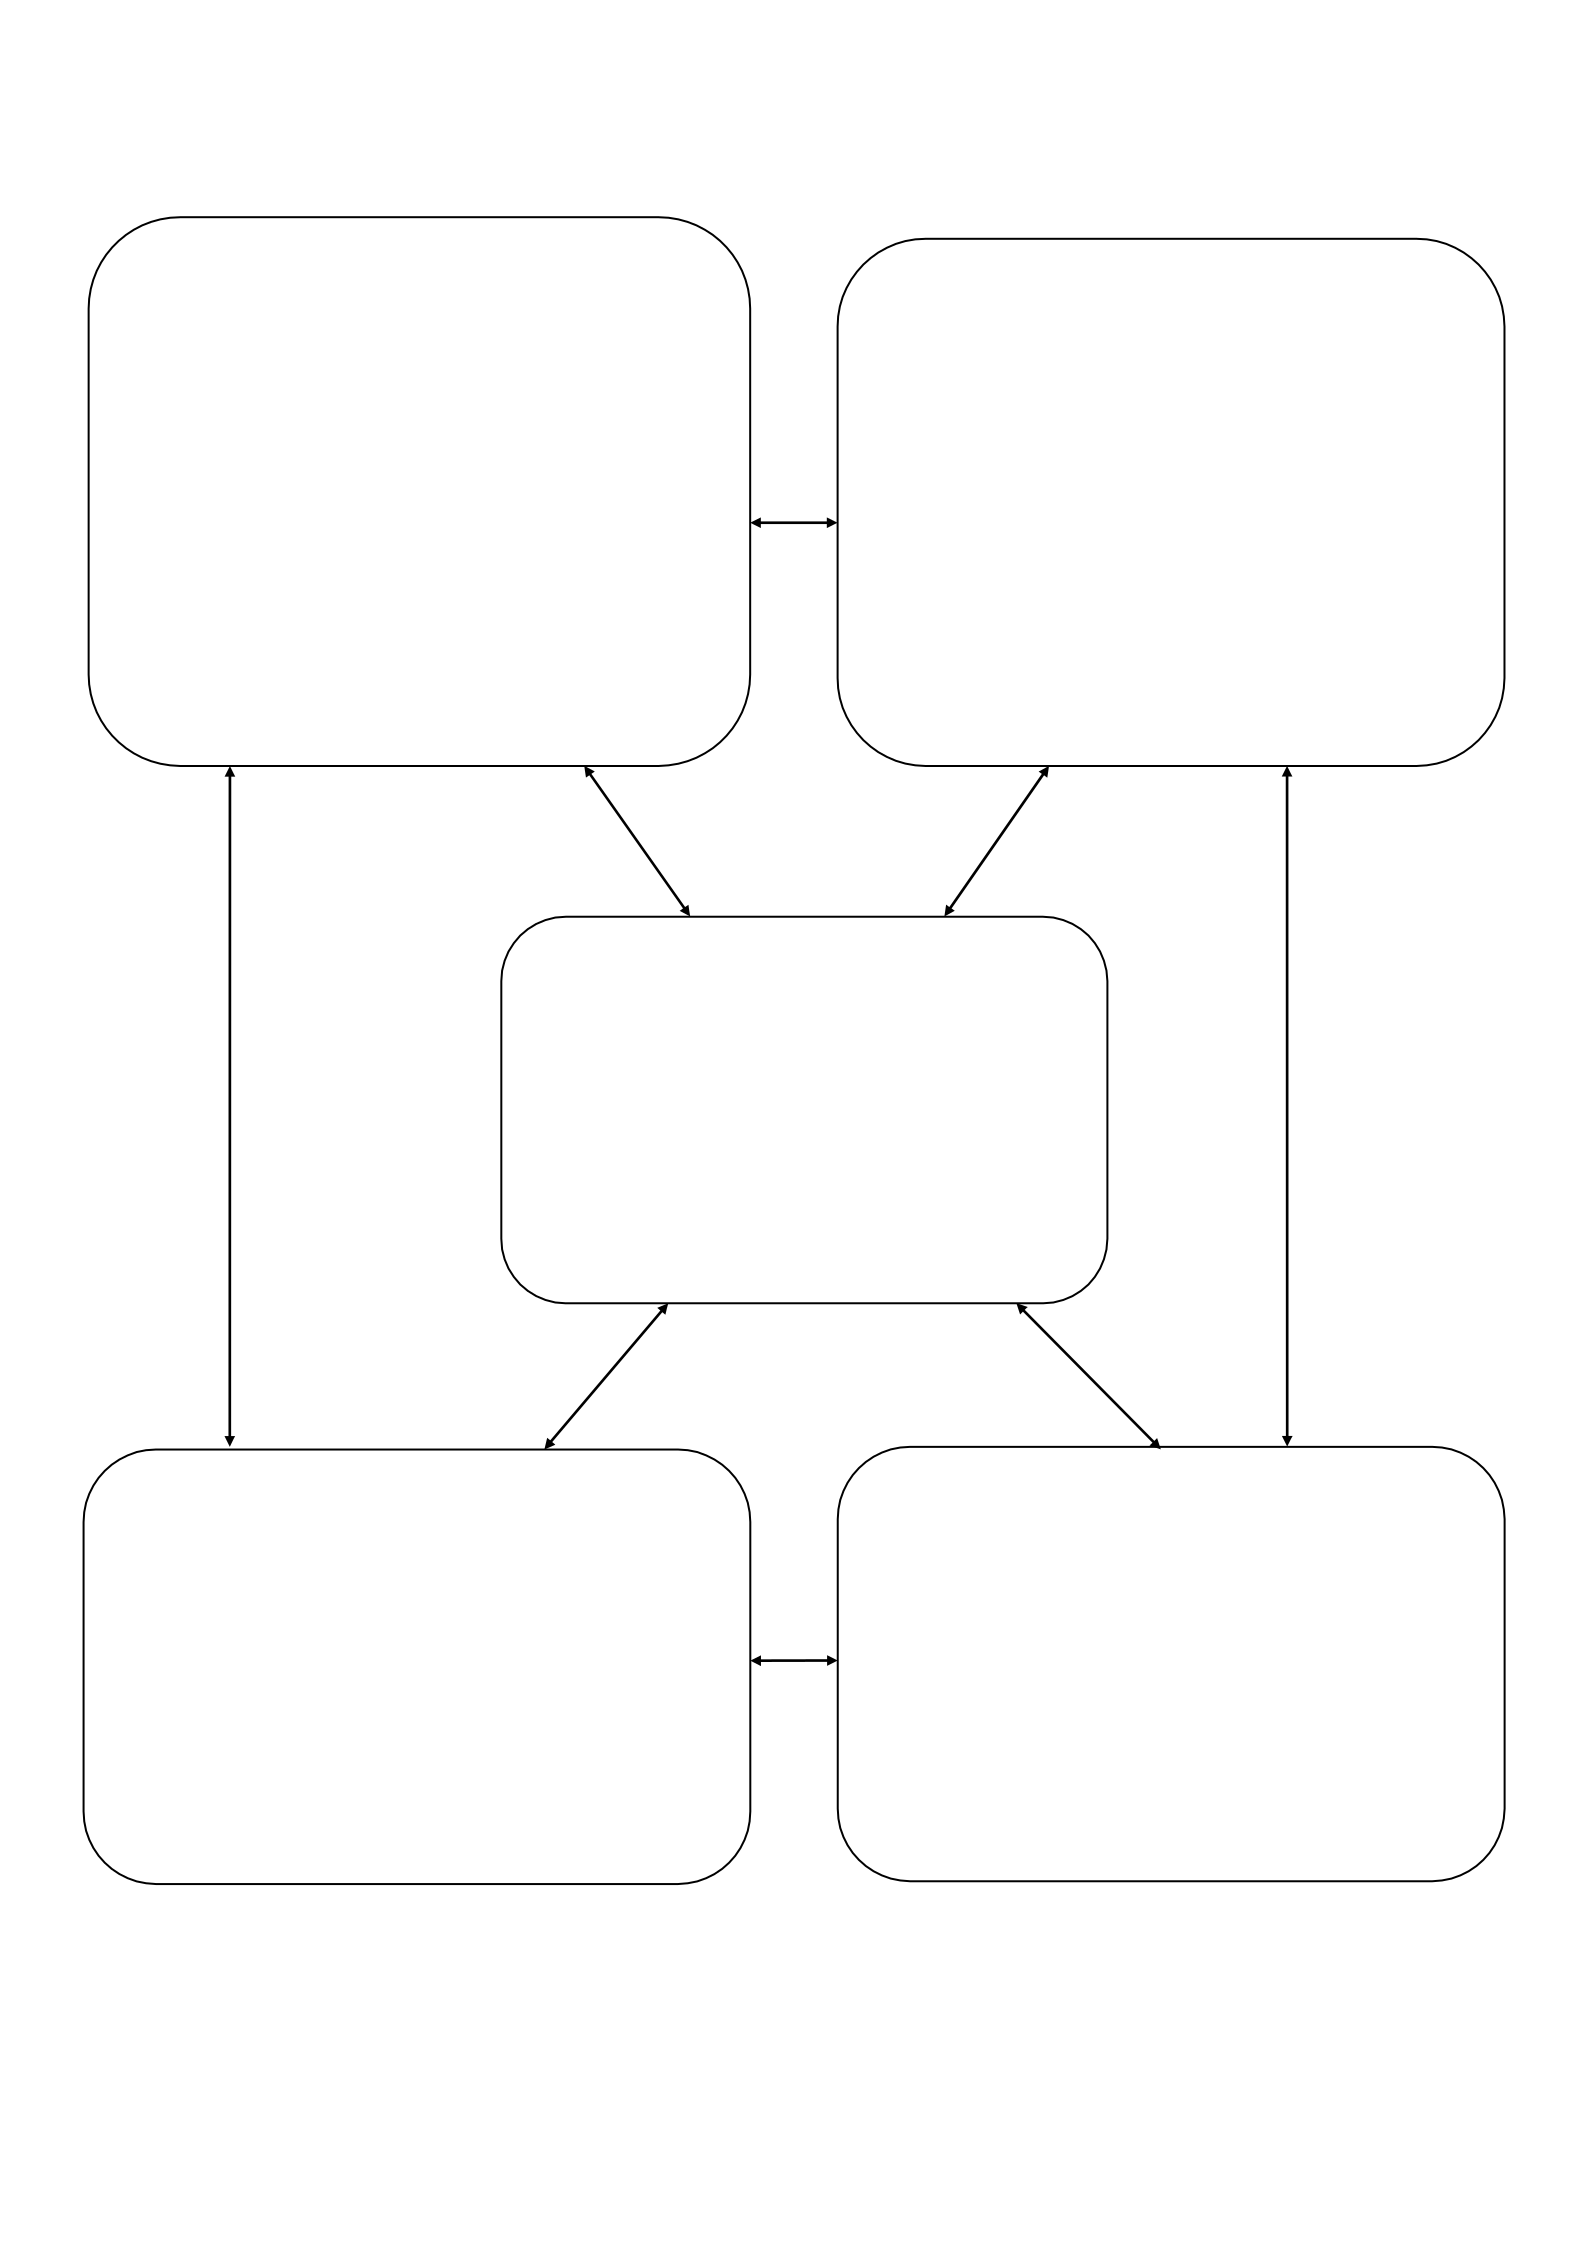
The researcher developed a conceptual framework which was adapted from Dagger et
al. (2007), and was based on various variables (Figure 1.7). These were divided into
independent and dependent variables. The first group of independent variables was
individual determinants including socio-demographic variables and patient health
characteristics. These include gender, age, place of residence, employment status,
highest level of education attained, marital status, health condition treated for, nature
of visit- first or return visit and physical disability- whether disabled or not. The
second group of independent variables was provider interpersonal aspects. These
include receiving adequate attention from healthcare providers, being served with
passion, being respected by staff, provision of personalized care, empathy and
understanding from hospital staff and effective communication. The third group in
this category was technical quality and provider competence. These include staff
knowledge and skills, adequate supervision of care process, observance of privacy
and confidentiality, duration of waiting time before service and the length of
consultation time. Hospital milieu was the final group in this category. It entailed the
hospital environment and includes accessibility of medical care, affordability of care,
convenience, cleanliness, appearance of physical facilities, presence of supplies and
services and hospital accreditation.
Patient satisfaction was taken to represent the outcome variable and aspects including
patient loyalty, recommendation of service to others and perceived service quality
were the operational dependent variables in this category.
8
Individual determinants:
1. Gender
2. Age
3. Residence
4. Employment status
5. highest level of education attained
6. marital status
7. health condition treated for
8. nature of visit- first or return
9. physical disability- yes or no
Provider Interpersonal aspects:
1. Attention
2. Passion to serve,
3. Respect for patients,
4. Provision of personalized care,
5. Sympathy and understanding,
6. Effective communication.
Patient satisfaction:
1. Patient loyalty
2. Recommendation of service to others
3. Perceived service quality
Technical quality and provider
competence:
1. Staff knowledge and skills
2. Adequate supervision of care
process
3. Privacy and confidentiality
4. Waiting time
5. Consultation time
Hospital milieu
1. Accessibility,
2. Affordability,
3. Convenience,
4. Cleanliness,
5. Appearance of physical facilities,
6.Presence of supplies and services
7.Hospital accreditation.
Figure 1.7: Conceptual frame
work Source : Dagger et al. (2007)

9
LITERATURE REVIEW
2.1. Introduction
Patient satisfaction is a key criterion by which the quality of health care services is
evaluated (Young et al., 2000). It can be defined as a state of pleasure or contentment
with an action, event or service, especially one that was previously desired (Ho rnsby
and Crouther, 2000). In medical care, patient satisfaction can be considered in the
context of patients’ appraisal of their desires and expectations of health care. It is the
subjective evaluation of the service received against the individual’s expectations
(Sitzia and Wood, 1997). Patients’ judgment of hospital service quality and their
feedback are essential in quality of care monitoring and improvement (Boyer et al.,
2006). There are two main dimensions of quality of care – access of care and patient-
centeredness. Accessibility can be defined as the opportunity or ease which
consumers or communities are able to use services in proportion to their need
(Whitehead, 1990). Patient centred care is defined as a deliberate attempt to
understand and flexibly respond to the patients’ perspective – their concerns and their
priorities as a whole person (Stewart, 2001). Patient satisfaction data are routinely
collected and used for continuous quality improvement by health care institutions and
hospitals in developed countries. While this is gaining momentum in a number of
developing countries especially in Asia (Andaleeb et al., 2007) the practice is,
however uncommon in African settings. Healthcare is the diagnosis, treatment, and
prevention of diseases, illness, injury, and other physical and mental impairments in
humans. Healthcare is delivered by practitioners in medicine, dentistry, nursing,
pharmacy, allied health and other care providers. It refers to the work done in
providing primary care, secondary care and tertiary care, as well as in public health

10
(Wikipedia contributors, 2012). Healthcare services consists of hospital care, family
or other physical care, community based care and tele- health services.
This literature review looks at patient satisfaction measurement, importance of
healthcare service attributes, patient satisfaction levels in various settings and some of
the significant factors that have been shown to influence patient satisfaction.
2.2. Patient satisfaction measurement
A critical aspect in the patient satisfaction’s measurement is that models and
instruments sometimes reflect the providers’ perspective rather than the patients’ one
(Calnan, 1988). For example, the patient capability to evaluate health services and
professionals’ skills is frequently questioned (Ben-Sira, 1976; Rao et.al. 2006), even
when these items receive high satisfaction rates. According to Hopkins et al. (1994),
patients are less capable of judging technical competence because of a real
informative asymmetry and in any case they are more reserved in expressing critical
comments with regard to the abilities of doctors. As a consequence, the high
satisfaction scores observed may depend on the confidence in doctors’ capabilities.
Instead, Coulter (2006) argued that well designed questionnaires allow assessing both
the technical competence and interpersonal skills of health professionals. The patient
satisfaction measurements have been generally used in order to provide researchers,
health managers and professionals with valuable information for understanding
patients’ experience, promoting patient’s compliance with treatment, identifying the
weaknesses in services and evaluating health service performance (Sitzia and Wood,
1997). Although the debate on the use of patient satisfaction as an outcome measure is
still open (Reker et al. 2002; Norquist, 2009), it has been observed that satisfied
patients are more compliant and more likely to participate in their treatment

11
(Guldvog, 1999). In fact, a satisfied patient is more aware of his care pathway and
more willing to follow the physician prescriptions.
The level of satisfaction depends on several and different elements. For instance,
healthy people tend to be more satisfied when they receive general information on
health services and on their quality; on the contrary, people with a chronic condition
may be more satisfied if involved in the decision- making process (Cleary and McNeil,
1997). Thus, the improvement of patient compliance requires adopting different
actions depending on the patient’s profile. The assessment of patient satisfaction with
the process of care is an important measure of the care quality and it allows
identifying the phases of the process to be improved. Questionnaires using report style
questions allows observation of how the care is delivered (Wensing et al., 2003;
Leeper et al., 2003). Some studies have highlighted that satisfaction strongly increases
when care is provided in accordance with the clinical standard procedures (Lantz et
al., 2005; Marchisio et al., 2006). Furthermore, the patients’ point of view may help
managers to evaluate activities such as the purchase of new technologies or the test of
new medical treatments (Hopkins et al., 1994; Dunlop et al., 2003; Ahmad et al.,
2008; Van Koulil et al., 2009). It is therefore critical that well designed questionnaires
should be used in the assessment of patient satisfaction. Moreover, necessary testing
should be carried out so as to ensure reliability and validity of the data collection
instruments.
2.3. Perceived importance of healthcare service attributes
In order to assess the level and determinants of client satisfaction with outpatient care,
it is important to know what attributes of healthcare quality are of importance to the

12
patients. Various studies have shown diverse health care service attributes that are
thought to be of great to clients.
A study in Germany identified ten such attributes as: outcome of treatment, kindness
of hospital nurses and physicians, organization of procedures and operations, quality
of food, accommodation, individualized medical care, discharge procedures and
instructions, physicians’ competence and cleanliness (Schoenfelder et al., 2011).
Other studies have shown that patients’ perceptions of quality are often influenced by
their interaction with the healthcare provider; the thoroughness with which the
providers examine and communicate with their patients (Meredith et al., 2008, and
Marcinowiz et al., 2009). Although the attributes are general in nature and do not
apply to any particular healthcare institution, they are an important indicator of what
patients expect from healthcare providers. They form a basis for the formulation and
design of instruments that assist in the assessment of client satisfaction with
healthcare services.
2.4. Patient satisfaction levels
Various studies have been done to ascertain levels of satisfaction with healthcare
services. Studies by (Schoenfelder et al., 2011; Meredith et al., 2008; Muhondwa et
al., 2008; Birhanu et al., 2010), have shown that most patients report satisfaction with
the care they receive both in public and private hospitals. However, contrary to the
findings of the researchers mentioned above, a client satisfaction study at Mulago
hospital in Uganda reported lower than normal clients’ general satisfaction (Sekandi
et al., 2011). Furthermore, a number of studies have sought to establish if there exists
a satisfaction level gap between public and private health facilities. A study carried
out in Hong Kong, (Wong et al., 2011) sought to look at the levels of client

13
satisfaction with public and private hospital care. The researchers presented results of
a population survey of 1,264 respondents in which the mean global satisfaction score
for public and private hospital care were 7.3/10 and 7.8/10 respectively. In the
Gambia, a cross-sectional study was done by Isatou et al. (2012) among 502 pregnant
women in six public and six private health facilities in a bid to assess women’s
perception of antenatal care services. The researchers reported satisfaction rates of
79.9% for public health facilities and 97.9% for private health facilities. A study
looking at client satisfaction with general health service s in Uganda reported that
clients of private health facilities expressed higher satisfaction than users of
government health facilities (Jitta et al., 2008). These findings are in agreement with
those of a patient satisfaction survey carried out by the ministries of health in Kenya,
in which a total of 2,018 patients sampled from both government health facilities and
faith based health facilities were interviewed. It was noted that government health
facilities had an overall lower score of 74% compared to 80% for faith based health
facilities. The disparity could be explained by a number of factors, for example, less
waiting time, availability of supplies and personalized care offered in private health
facilities. It is believed that patient satisfaction levels may vary from one setting to
another, and is a product of the determinants of satisfaction. There seems to be a
systematic trend in which the levels of patient satisfaction are lower in public
hospitals compared to those in private ones.

14
RESEARCH METHODOLOGY
Introduction
This chapter described the research methodology that was used in the study. These
included study setting, study design, target population, the sample size and sampling
procedure to be used. It further explained the data collection methods and tools
employed in the study and data management and analysis methods. Finally, the
chapter specified the ethical requirements followed throughout the period of data
collection and after data collection and the study limitations.
Study Setting
The study was carried out at Busia District Hospital. It is located in Busia town, in
Busia district, in Kenya’s Western province, approximately 268 miles (431
kilometers), by road west of Nairobi, Kenya’s capital city. It is located near the
Kenya-Uganda border. The district has a population of 488,075 (Ministry of Planning,
National Development and Vision 2030, 2009), but this has reduced following the
curving out of 3 more districts out of the larger Busia district. Busia district hospital is
the largest district hospital in Busia County, with a bed capacity of 164 and also
serves a considerable number of patients from the neighboring Uganda. The hospital
is one of the largest level 4 hospitals in Kenya. Some of the services offered at this
hospital include antenatal care, basic emergency obstetric care, caesarean section,
comprehensive emergency obstetric care, curative inpatient services, curative
outpatient services, family planning, growth monitoring and promotion, HIV
counseling and testing, home based care, immunization, integrated management o f
childhood illnesses, prevention of mother to child transmission of HIV, radiology

15
services, laboratory services, and youth friendly services. According to the hospital’s
health records information officer, an average of 4,988 patients were served monthly
at the various outpatient clinics and service delivery points. Over the last 2 years, the
highest number of patients served in the outpatient department was 6,554.
Study design
An institution based cross- sectional study design was utilized. This is a descriptive
study that involves measuring different variables in the population of interest at a
single point in time. This design was suited for this study since the study was
descriptive in the form of a survey to describe a subgroup within the hospital’s patient
population with regard to determinants of patients’ satisfaction. Among the study
design’s advantages include the following:
(i) Ease of data gathering and assessment even for large target populations.
(ii) The low to moderate cost makes it possible to conduct more thorough
investigations of the population’s overall condition.
Some of its disadvantages include the following:
(i) Questionnaires introduce a previous incidents’ bias called Neyman bias. Even
if a researcher uses a completely objective questionnaire, the respondent
cannot answer questions involving past events with perfect accuracy. This
either magnifies or minimizes the effects of certain variables, thereby affecting
the study’s results.
(ii) Confounding factors. Additional variables may affect the relationship between
the variables of interest but not affect those variables themselves.

16
Study population
The study population comprised of all patients who visited the Busia district hospital
for treatment during the study period. The patients who attend the hospital come from
the entire Busia County as well as the neighboring Uganda. The highest number of
patients served in the outpatient section over the last 2 years was 6,554, which was
taken to be the target population.
Inclusion Criteria
Respondents who met the following criteria were included in this study:
i. Those of legal age (18 years and above), who were able and willing to
provide written or verbal consent in English or Kiswahili.
ii. Parents or guardians of patients below the age of majority (18 years), who
gave consent to the interview.
iii. Parents or guardians of patients who were incapacitated, who gave consent to
the interview.
Exclusion criteria
Respondents who met the following criteria were excluded from the study:
i. Patients who were critically ill.
ii. Patients in the in-patient section of the facility.

17
Sample size determination
Fisher’s method was used in sample size determination using the formula (Fisher,
1998), based on the following assumptions:
i) That 50% of the patients would report being satisfied with the outpatient
services provided (this is because there were no prior published studies on
patient satisfaction at Busia District Hospital or any other similar setting).
ii) A 5% level of statistical significance.
iii) A target population of approximately 6,554 patients, the highest number
treated in a month over the last 3 years.
iv) A 10% non-response rate adjustment.
The formula was:
n = z2pq÷d2
Where;
n=desired sample size (if the target population is greater than 10,000)
z = the standard normal deviation at the required confidence level (in this case 1.96)
p= the proportion in the target population estimated to have the existing variable
being measured.
q = 1-p
d = the level of statistical significance set.
The sample size for a population more than 10,000 would thus be;
n = (1.96)2(0.5) (0.5) ÷ (0.05)2
= 384

18
Since the targeted population was below 10,000 (the highest number of patients
attended to in a month over the last two years was 6,554), the final sample size (nf)
was then calculated as follows:
n f = n ÷ {1+ (n/N)}
Where;
n f = desired sample size (when target population is less than 10,000)
n = desired sample size (when target population is greater than 10,000)
N = the desired sample size (target population)
Therefore, n f = 384 ÷ {1+ (384/6554)}
= 362.75
Adjusting for non-response at 10% (Abraham et al., 2006) gave a required sample
size of 399, which was approximated to 400.
Sampling procedure
Systematic random sampling method was used to select respondents. The
approximate target population of 6,554 patients was divided by the required sample
size, 400 to get the sampling interval of 16. The first patient was selected at random
and every 17th patient who met the inclusion criteria was interviewed until the total
number of 400 patients was reached.
Data collection procedures
The researcher utilized a structured questionnaire. This was divided into sections that
included background information of the respondents, general patient satisfaction,
satisfaction with specific services received, importance of service attributes, and

19
assessment of technical quality and provider competence, provider interpersonal
aspects, hospital milieu/environment and patient’s loyalty to the health facility.
Measurement of variables
a) Dependent variable
The dependent variable was “Client satisfaction with outpatient healthcare services at
Busia District Hospital”. The level of patient satisfaction was measured based on key
outpatient service areas of the health facility’s OPD, as well as the general patient
satisfaction with OPD services. In this context, a 5-point Likert scale ranging from
“strongly agree” (5) to “strongly disagree” (1), was used and this was done for all the
key outpatient services offered in the health facility.
b) Independent variables
In this study, variables considered as potential independent predictors of the outcome
were divided into two groups, namely;
i) Individual determinants; including age, gender, place of residence,
employment status, highest level of education attained, marital status and
health status.
1. Gender; was recorded as either male or female.
2. Age; was recorded into clusters of 18-25 years, 26-35 years, 36-45
years, 46-55 years, 56-65 years and over 65 years. There was also a
record for those who did not know their age.
3. Highest level of education attained; was indicated as no formal
schooling, primary education, secondary education, post-secondary
education, college education or university education.

20
4. Employment status; was indicated as permanent employment, casual
employment, self employed or unemployed.
5. Place of residence; a record of respondents’ place of residence was
done in an attempt to approximate the distance from the health facility
and whether it was within Busia town or outside.
6. Health status; a record of the diagnosis (if known to the respondent)
and whether the respondent was physically disabled or not.
7. Nature of visit; whether it was a first visit or a return visit.
ii) Service provider related determinants; including
1. Technical quality and provider competence e.g. skill and knowledge of
health workers, availability of medicines and other supplies, waiting
and service time, and provision of medical education to patients. This
was measured using 7 items assessed on a 5-score Likert scale and 2
items to record waiting time and service time.
2. Provider interpersonal aspects e.g. communication with patients,
respect, observing privacy and confidentiality, sympathy and
understanding, and involvement of patients in decision- making. These
were measured using 11 items assessed on a 5-score Likert scale.
3. Hospital milieu e.g. accessibility, availability and convenient of care,
affordability of care, cleanliness and the physical appearance of the
facility. These were measured using 9 items assessed on a 5-score
Likert scale and 2 items to record payments made at various service
points and whether patients thought they were affordable or expensive.

21
3.2. Quality Assurance
The questionnaire was examined by the research sponsors who provided suggestions
for correction. A pilot test was done to check its adaptability. A preliminary study was
conducted prior to the main study and the data collected statistically analyzed to
establish reliability and validity. The questionnaire was found to be psychometrically
sound across multiple tests of reliability and validity. The instrument was validated on
tests of content, construct and criterion validity and was found to be internally
consistent. The questionnaire consisted of five internally consistent scales – level of
patient satisfaction, perceived importance of healthcare service attributes, perceived
technical quality, perceived interaction quality and perceived environment quality.
The internal consistency of each scale was assessed by item- total correlations and
Cronbach’s Alpha. All the questions using the 5–point Likert scale exceeded the
criterion 0.70 Cronbach’s alpha standard for reliable measures. The Cronbach’s Alpha
coefficient for the entire questionnaire was 0.910.
Pre-testing of the questionnaire involved a trial run with a group of respondents with
the aim of detecting problems in the questionnaire’s instructions or design. The
questionnaire was evaluated at this stage for evidence of ambiguous questions,
potential misunderstandings, and evidence that the question meant the same thing to
all respondents. At the end of each day, questionnaires were checked for errors and
missing data in order to rectify this while still at the study site.

22
3.8. Data management and Analysis
3.8.1. Data management
Data collected was cleaned, edited and coded to avoid incompleteness during entry.
Minor mistakes committed during data collection were corrected in the field. Upon
the completion of data collection and editing in the field, systematic organization of
raw data was done to facilitate data analysis. Questionnaires with missing variables,
information or mistakes were left out. This resulted in the exclusion of 4
questionnaires (1%). Data collected was always in the custody of the trained research
assistants when in the field before surrendering them to the researcher. The
administered questionnaires were presented to the researcher every day after each
day’s work. To ensure that all the questionnaires were returned back to the researcher,
every research assistant had to account for all the issued questionnaires and the spoilt
questionnaires were to be given back to the researcher.
3.8.2. Data analysis
Data were cleaned, edited, coded and entered into SPSS version 18. Using SPSS
version 18, descriptive statistics were used to determine indices. Factor analysis was
done to identify factors that explained most of the variance observed in the popula tion
with regard to each scale. Multiple linear regression analysis for identifying
determinants of outpatient satisfaction at the healthcare facility was done. A
significance level of 0.05 was used in all cases.
Factor analysis was employed for all Likert scale instruments to extract factor(s)
representing each of the scales and have factor scores, which facilitate treatment of
the variables as continuous during further analysis. During all factor analysis

23
procedures, principal axis factoring with Eigen value greater than or equal to one
extraction and Varimax rotation methods were employed. Whenever the scales had
more than one factor extracted the factors were renamed using appropriate
abbreviations according to the items contained in the factor extracted.
3.9. Ethical Considerations
The study was approved by the Kenyatta National Hospital/University of Nairobi
Ethics and Research Review Committee. Further approval was obtained from Busia
District Hospital’s medical superintendent and finally informed consent from the
participants themselves. Participants were guaranteed confidentiality of the
information collected. Non-participation would not have a negative effect on care
given to patients. Confidentiality of data was maintained by use of identification
numbers rather than names and limiting access to the data. The study involved
minimal risks and privacy was maintained by carrying out interviews in an area
separate from where the other clients were waiting for services.
3.10. Limitations of the study
a. The study relied on questionnaires which are susceptible to response bias.
However, attempts were made to minimize this potential source of bias by
testing the tool, training field assistants on its administration, and amending it
to make the wording familiar.
b. This study also relied upon respondents’ recorded morbidity/ diagnosis. Hence
the data did not capture biomedical variables such as the perceived severity of
the illnesses reported, which might influence significantly, the patients’
satisfaction with care given.

24
c. The last week of data collection coincided with the start of a two month long
nurses’ strike and this could have influenced patients’ satisfaction with care
given.
d. Patients may experience a relatively short- lived ’halo effect’ whereby they feel
more satisfied immediately after their consultation than they do afterwards.
e. The reliance on the response of parents or caregivers for their children might
introduce surrogate bias.

25
RESULTS
4.1. Introduction
This chapter presents findings of the study under thematic areas namely respondents’
characteristics, importance of healthcare service attributes, general outpatient
satisfaction, service quality perspective and finally, the relationship among
respondents’ characteristics, service quality perspective and general outpatient
satisfaction. Factor analysis was employed for all Likert scale instruments. Principal
axis factoring with Eigen value greater than or equal to one extraction and Varimax
orthogonal rotation methods were employed. Factors extracted were renamed using
appropriate abbreviations according to the items contained in the factor extracted.
Multiple linear regression analysis for identifying determinants of outpatient
satisfaction at the healthcare facility was done. A significance level of 0.05 was used
in all cases. In regression analysis, beta (standardized) coefficient was used since it
uses a standard unit that is the same for all the variables in the equation.
4.2. Characteristics of Study Participants
This section presents the personal data of 396 clients, who visited Busia district
hospital outpatient department between 7th January and 1st February, 2013. In this
study, 400 respondents were sampled. However, 4 of the filled questionnaires were
faulty and only 396 were included in the analysis. In the study population, there were
160(40.4%) males and 236(59.6%) females as indicated in table 4.20. Majority of the
respondents were between the ages of 18 and 25 years (34.6%). A significant
proportion of the respondents had post-secondary schooling education (36.1%), while
the unemployed were the majority at 49%. Respondents who were on a return visit

26
were the majority at 68.2% and a significant number of them lived within
approximately two kilometers radius of the healthcare facility (66.9%). Respondents
who were treated for acute illnesses and injuries comprised the majority at 72.7%.
Table 4.21 Characteristics of respondents
Respondents’ characteristics
Frequency Percentage
Gender: Male
Female
Age:
18-25 years
26-35 years
36-45 years
46-55 years
56-65 years
Over 65 years
Do not know
Highest education: No formal education
Primary education
Secondary education
Post- secondary education
Employment status: Permanent employment
Casual employment
Self employed
Unemployed
Marital status: Married
Single
Divorced
Physically disabled: Yes
No
Nature of visit:
First visit
Return visit
Place of residence: Within 2km radius of hospital
Beyond 2km radius of hospital
Nature of illness:
Enquiries, screening, MCH/FP visits
Acute illnesses and injuries
Chronic illnesses
160
236
137
132
58
27
26
11
5
24
123
106
143
59
49
94
194
248
135
13
34
362
126
270
265
131
31
288
77
40.4
59.6
34.6
33.3
14.6
6.8
6.6
2.8
1.3
6.1
31.1
26.8
36.1
14.9
12.4
23.7
49.0
62.6
34.1
3.3
8.6
91.4
31.8
68.2
66.9
33.1
7.8
72.7
19.4
27
4.3. Perceived Importance of Healthcare Service Attributes
In order to address specific objective one which sought to assess the importance of
healthcare service attributes, twelve items were tested as measures of perceived
importance of healthcare service attributes. These items were subjected to hierachical
regression to establish which attributes best explained the importance of healthcare
service attributes. Descriptive statistics were run for all the items to assess for the
accuracy of entry of data, mean score for each item and normality as shown in Table
4.31. High means above average were recorded across all item measures with three
items, attribute 4, attribute 7 and attribute 10 registering the lowest means.
Table 4.31 Descriptive Statistics for importance of healthcare service attributes
Attributes Mean Standard
De vi
ation
Skewness
Friendly staff
Knowledge and competence
Respect from staff
Gu idance and information
Cleanliness and tidiness
Appearance of staff
Cost of healthcare
Privacy and confidentiality
Accessibility and availability
Waiting time before service
Availability of medical supplies
Consultation time
4.46
4.72
4.38
3.49
4.35
4.43
3.98
4.22
4.01
3.33
4.53
4.17
.694
.574
.765
1.619
.711
.614
1.180
.901
1.170
1.321
.901
.913
-1.361
-2.396
-1.383
-.538
-.996
-.848
-.835
-.875
-.863
-.151
-2.243
-.798
The twelve items were then subjected to hierachical regression to establish which
healthcare service attributes were most important to patients. The initial analysis
focused on test for sampling adequacy using K.M.O’s test of sampling adequacy and

28
Bartlett’s test of sphericity for all attributes. KMO measures the sampling adequacy
which should be greater than 0.5 for a satisfactory factor analysis to proceed. The
results indicated that the sample size was adequate (KMO=0.887; χ2=2189.012;
df=66; p<0.05). Bartlett’s test is an indication of the strength of the relationship
among variables. It tests the null hypothesis that the correlation matrix is an identity
matrix. This was found to be significant since its associated probability is less than
0.05. Further analysis was done to determine and extract factors that would explain
the importance of healthcare service attributes based on the twelve attributes. A total
of twelve factors were possible to be extracted but only two factors met the criteria of
eigen values set at one, namely HCSA1 and HCSA2. The rest of the factors were not
valid. Eleven out of twelve attributes emerged as measures of importance of
healthcare service attributes, accounting for 48.6% of the variance. HCSA1 which
constituted items related to the friendliness of hospital staff, knowledge and
competence of staff, treating patients with respect, cleanliness and tidiness of the
health facility, and overall appearance of the staff accounted for 24.56 % of the
variance, followed by HCSA2 which accounted for 23.99% and consisted of seven
items measuring the perceived importance of friendliness of hospital staff, guidance
and information provided on patients’ health needs, cost of healthcare, privacy and
confidentiality, accessibility and availability of healthcare, waiting time before service
and time spent with the healthcare provider. This has been displayed in Table 4.32
and Figure 4.32.
29
Table 4.32 Rotated factor matrix for Importance of healthcare service attributes
Attributes Factor
SA1 SA2
1
Friendliness of hospital staff
.690
2
Knowledge and competence of staff
.630
3
Treating you with respect .787
4
Gu idance/information provided on health issues
.685
5
Cleanliness and tidiness of health facility
.689
6
Overall appearance of the staff
.614
7
Cost of healthcare
.534
8
Privacy and confidentiality during treatment .557
9
Accessibility and availability of healthcare
.713
10 Waiting time before service 593
11 Availability of medicines and other medical supplies
12
Time spent with the healthcare service provider
.597
Overall variance explained was 48.6%
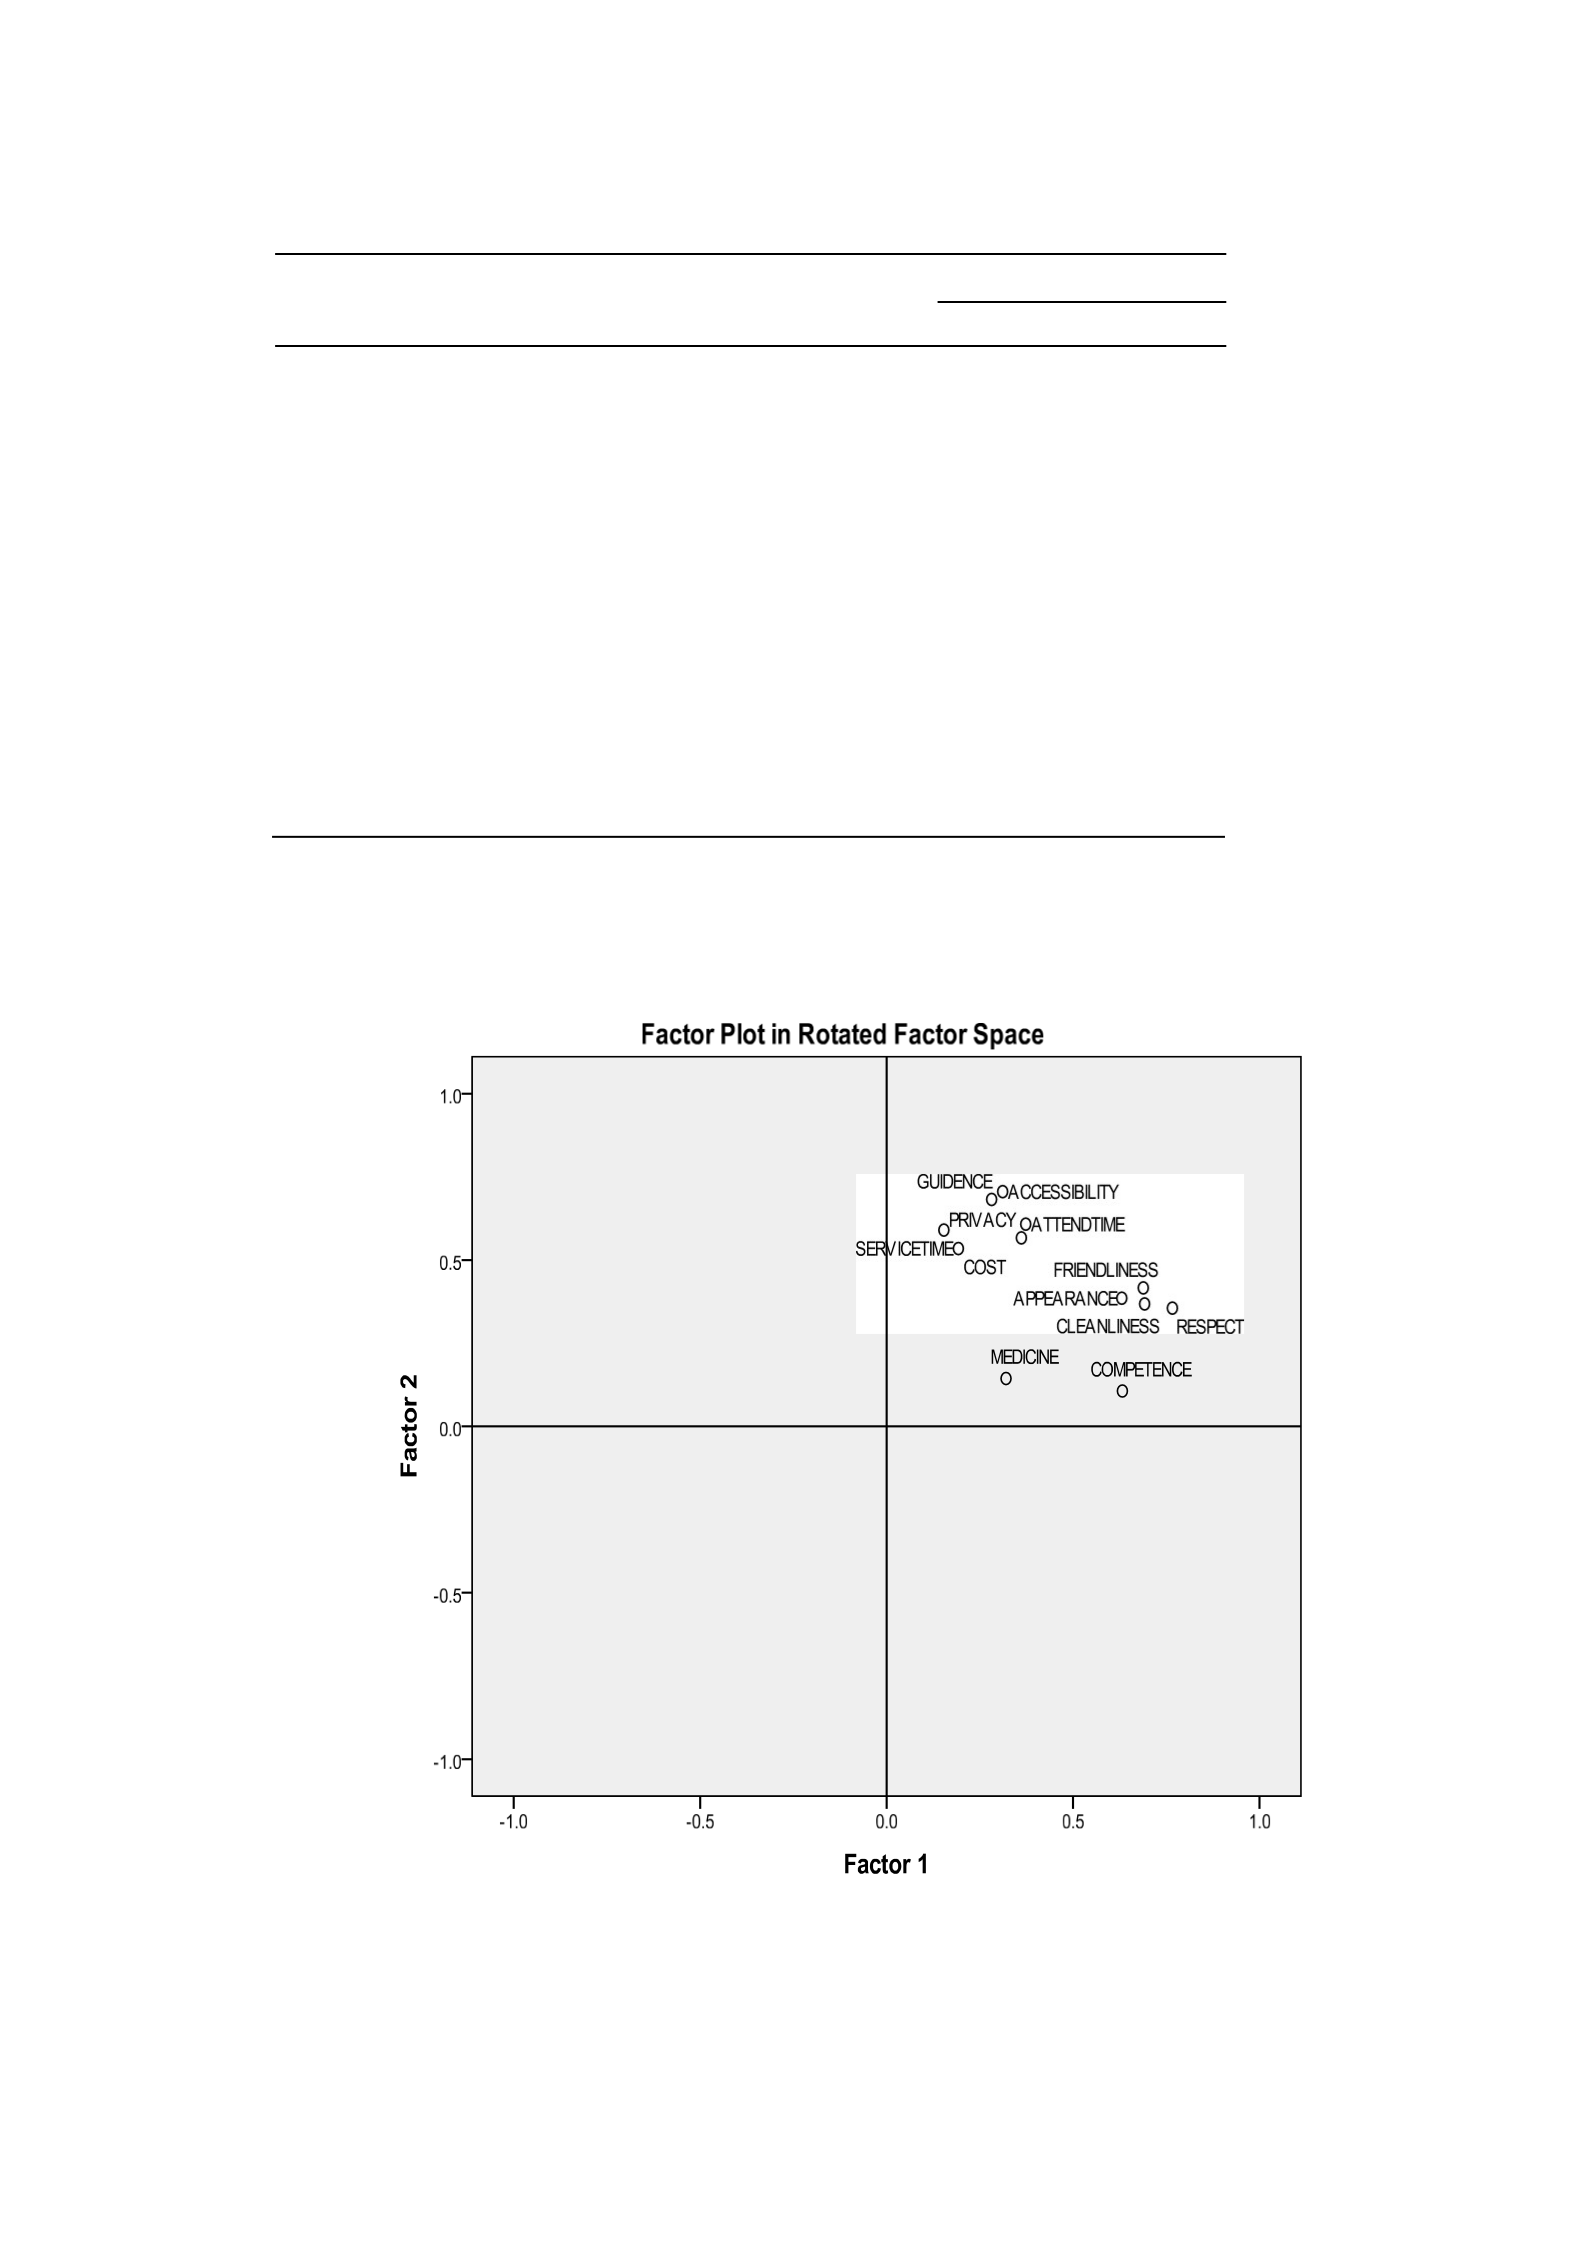
In order to show the distribution of the rotated factors, all the items were loaded into a
factor space and displayed in Figure 4.31.
Figure 4.31 Distribution of importance of healthcare service attributes items into
factor space

30
Further analysis was done to show the magnitude of predictors of Factor 1. The
results indicated that the five items including friendliness of hospital staff, knowledge
and competence of staff, staff treating you with respect, cleanliness and tidiness of
health facility, and finally overall appearance of the staff significantly explained up to
89.8% of the total variance in importance of healthcare service attributes category-1
(R=0.898, F=325.606, p<0.05) as shown in Table 4.33. It emerged that being treated
with respect by hospital staff was the best predictor of importance of healthcare
service attributes category- 1 (β=0.401, t=10.483, p<0.05). This was followed by
knowledge and competence of staff (β=0.317, t=11.363, p<0.05) which was then
followed by cleanliness and tidiness of the facility (β=0.214, t=6.390, p<0.05) and
finally friendliness of hospital staff (β=0.099, t=2.835, p<0.05). The overall
appearance of hospital staff was not a significant predictor of importance of
healthcare service attributes category-1(β=0.051, t=1.656, p=0.098).
Table 4.33 Regression Analysis of importance of healthcare service attributes
category-1
Factor1
Model
Unstandardized
coefficients
Standardized
Coefficients
T
Sig.
B
Std. Error Beta
1
(Constant )
Attribute1
Attribute2
Attribute3
Attribute5
Attribute6
-8.285
.164
.634
.601
.346
.096
.246
.058
.056
.057
.054
.058
-33.714
2.835
11.363
10.483
6.390
1.656
0.000
0.005
0.000
0.000
0.000
0.098
.099
.317
.401
.214
.051

31
Similarly, analysis was done to display the strength of predictors of factor 2. The six
measures of importance of healthcare service attributes category-2 significantly
accounted for up to 91.2 % of the variance (R=0.912, F=320.291, P< 0.05). Table
4.34 shows that the most powerful predictor of importance of healthcare service
attributes category -2 was accessibility and availability of healthcare (β=0.341,
t=11.886, p<0.05), followed by guidance and information provided on health issues
(β=0.286, t=10.293, p < 0.05). This was followed by waiting time before service
(β=0.244, t=9.613, p < 0.05), the followed by cost of healthcare (β=0.159, t=6.381,
p<0.05), followed by time spent with the healthcare provider (β=0.097, t=3.610,
p<0.05) and finally, maintaining privacy and confidentiality during treatment
(β=0.074, t=2.832, p<0.05).
Table 4.34 Regression analysis of importance of healthcare service attributes
category-2
Model
Unstandardized
coefficients
Standardized
Coefficients
T
Sig.
B
Std. Error Beta
1
(Constant )
Attribute4
Attribute7
Attribute8
Attribute9
Attribute10
Attribute 12
-4.385
.208
.159
.096
.343
.217
.125
.140
.020
.025
.034
.029
.023
.035
-31.356
10.293
6.381
2.832
11.886
9.613
3.610
0.000
0.000
0.000
0.005
0.000
0.000
0.000
.286
.159
.074
.341
.244
.097

32
4.4. General Satisfaction with Outpatient Healthcare Service
In order to address specific objective two which sought to determine the general level
of patient satisfaction with outpatient healthcare services in Busia District Hospital,
Kenya, four items were tested as measures of overall satisfaction. These included
attribute 1 (the service I have received is excellent), attribute 2 (I am satisfied with the
medical care I received), attribute 3 (I have received the best healthcare as I expected)
and attribute 4 (I feel satisfied by the way I was treated by staff). These items were
subjected to hierachical regression to establish which items best explained general
satisfaction with outpatient healthcare services. Descriptive statistics were run for all
the items to assess for the accuracy of entry of data, mean score for each item and
normality. High means above average were recorded across all item measures (Table
4.41).
Table 4.41 Descriptive statistics for general outpatient satisfaction
Attributes Mean Standard
De vi ation
Skewness
Excellent service
Satisfied with medical care
Received best healthcare
Satisfied with treatment by staff
4.21
4.20
4.16
4.20
.875
.919
1.051
1.024
-1.179
-1.253
-1.382
-1.455
The initial analysis focused on test for sampling adequacy using K.M.O’s test of
sampling adequacy and Bartlett’s test of sphericity for all attributes. The results
indicated that the sample size was adequate (KMO=0.789; χ2=1086.563; df=6;
p<0.05). Further analysis was done to determine and extract factors that would
explain the nature of satisfaction based on the four attributes. A total of four factors
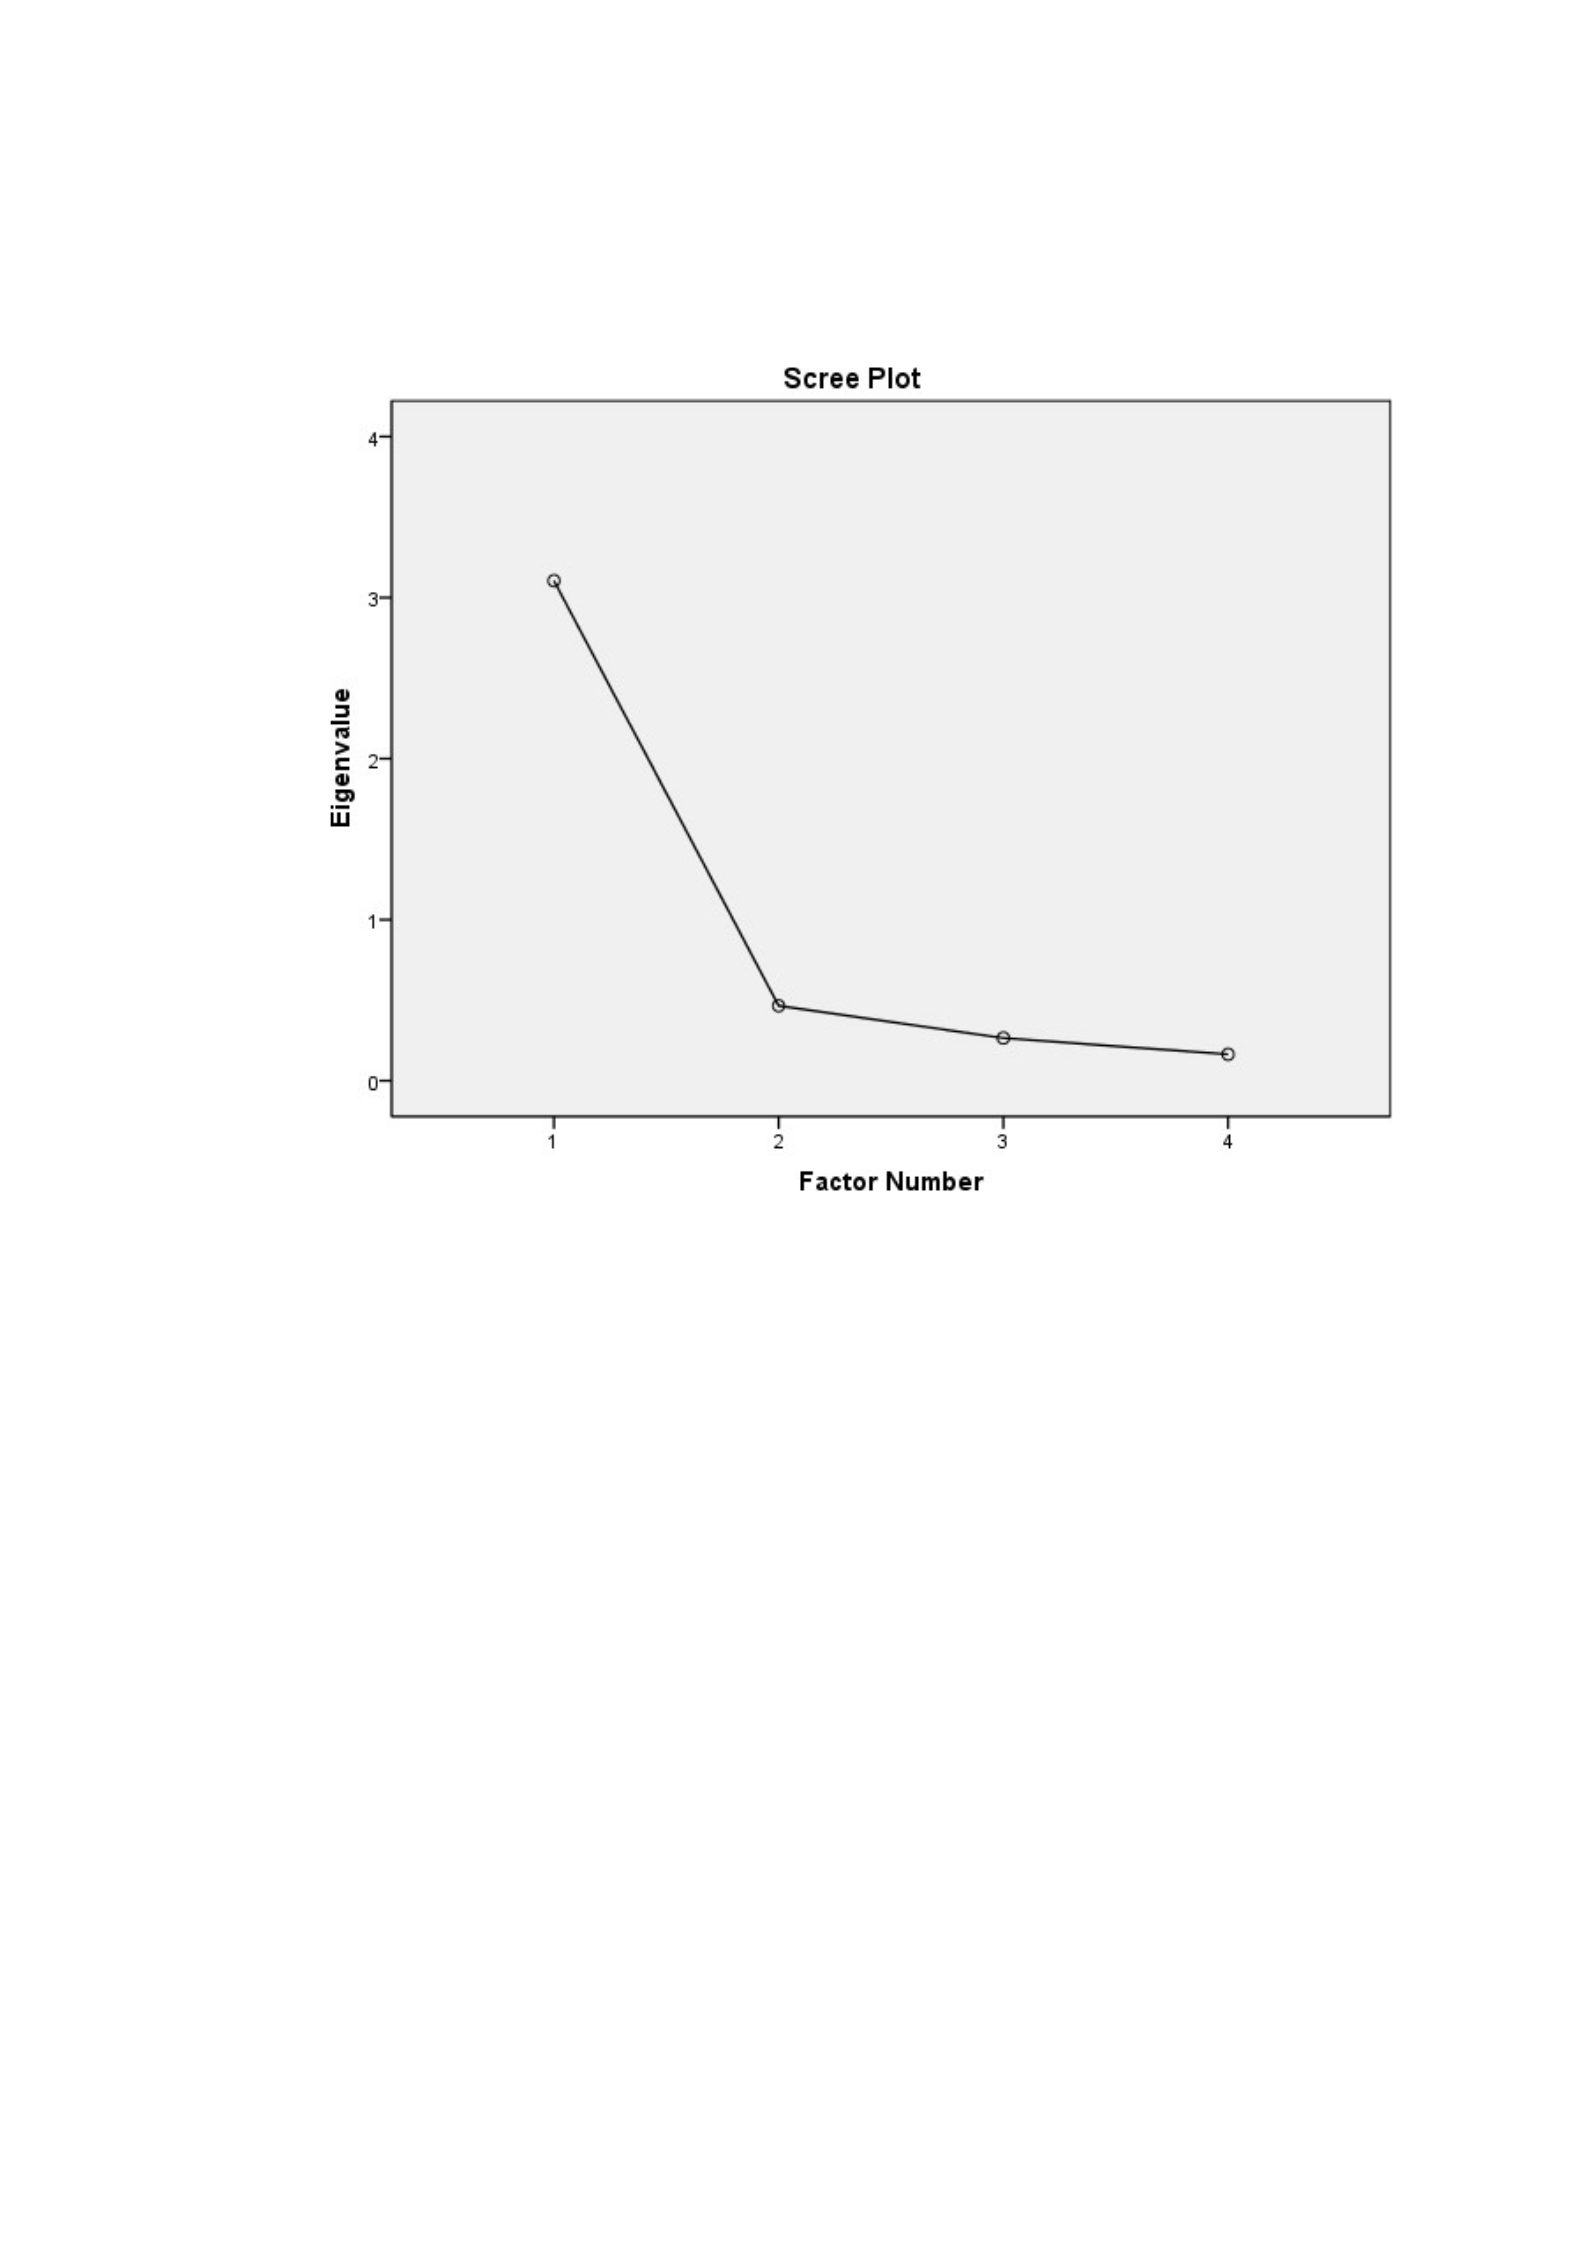
33
were possible to be extracted but only one factor met the criteria of eigen values set
at one as shown in Figure 4.41.
Figure 4.41: Scree plot for general outpatient satisfaction
The above scree plot is a graph of the eigenvalues against all the factors. It is useful
in deternining how many factors to retain. The curve begins to flatten from factor 2
all the way to factor 4. Factors 2, 3 and 4 have eigenvalues less than 1, so only factor
1 has been retained. The rest of the factors were not valid. All the attributes emerged
as measures of satisfaction, accounting for 70.3% of the variance of satisfaction as
shown in Table 4.42.

34
Table 4.42 General outpatient satisfaction rotated factor matrix
Attributes Factor1
All things considered, the service I have received from the health facility is e xce llent
I am satisfied with the medical care I have received
I have received the best healthcare as I expected from the health facility today
I feel satisfied with the way I have been treated by the health providers at the facility
.876
.868
.774
.833
Overall variance explained was 70.3%
Finally the extracted factors that depicted satisfaction were subjected to linear
regression to determine which of the attributes were the best significant predictors of
satisfaction. During this analysis, attribute 3 was dropped as it was similar to attribute
1. The three predictors could account for 99.3% variance of satisfaction (R=0.993;
F=9164.946; p<0.001). For the three attributes, the best area of satisfaction was found
in attribute 1 (β=0.399; t=35.619; p<0.001), followed by attribute 4 (β=0.352;
t=40.822; p<0.001) and finally attribute 2 (β=0.341; t=30.019; p<0.001). Table 4.43
shows that the level of patient satisfaction depended on attributes 1,4 and 2.

35
Table 4.43 Regression Analysis of general outpatient satisfaction category - 1
Model
Unstandardized
coefficients
Standardized
Coefficients
T
Sig.
B
Std.
Error
Beta
(Constant ) -5.171 .032 -161.651 0.000
Attribute1 .479 .013 .399 35.619 0.000
Attribute2 .390 .013 .341 30.019 0.000
Attribute4 .361 .009 .352 40.822 0.000
Further analysis was done on the extracted items measuring level of general
satisfaction with healthcare service to determine whether there was any significant
difference between respondents who agreed and those who disagreed with each of
the items. Scores of “agree” and “strongly agree” were taken to imply satisfaction.
Similarly, scores of “disagree’ and “strongly disagree” were taken to imply
dissatisfaction. A two-tailed z-test at 5 percent level of significance (p-value< 0.05)
was carried out as shown in Table 4.44.

36
Table 4.44 General level of satisfaction with outpatient healthcare services
Attributes
Proportion
Satisfied
(n)
Proportion
Dissatisfied
(n)
z-test p-value
1
The service I have received is e xcellent
84.6(335) 6.1(24) 9.2 0.0000
2
I am satisfied with the medical care I have
received
84.6(335) 7.8(31) 9.9 0.0000
4
I feel satisfied the way I was treated by the staff
84.4(334) 10.1(40) 10.5 0.0000
According to the results, there was significant difference for all the items extracted as
key measures of general satisfaction with outpatient healthcare services. Majority of
the respondents were significantly satisfied as regards items 1, 2 and 4.
Further analysis was done to determine whether there was any significant difference
between the observed proportion of respondents who reported satisfaction and the
expected level of satisfaction among the study population. It was assumed that
approximately 50% of the study population was satisfied with outpatient healthcare
services. A 1-sample z-test for a population proportion at 5 percent level of
significance (p-value< 0.05) was used and the results are as shown in table 4.45

37
Table 4.45 General level of satisfaction with outpatient healthcare services in
comparison to the expected population satisfaction
Observe d
Proportion
Satisfied
(n)
Expected
population
satisfaction
z-test p-value
Attributes
1
The service I have received is e xcellent
84.6(335) 50.0 12.7 0.000
2
I am satisfied with the medical care I have
received
84.6(335) 50.0 12.7 0.000
4
I feel satisfied the way I was treated by the staff
84.4(334) 50.0 12.6 0.000
From the results on Table 4.45, it is evident that there is significant difference
between the expected level of satisfaction in the study population and the observed
level of satisfaction with outpatient healthcare services. This implies a much higher
level of satisfaction than expected.

38
4.5. Patients’ Perceived Service Quality
In order to address specific objective three which sought to identify the factors
associated with the level of patient satisfaction in Busia District Hospital, Kenya,
factor analysis technique was also employed to achieve this objective. This involved
the use of pricinple axis factoring which utilized Varimax as the mode of rotation.
Besides socio-demographic factors and patients’ health characteristics, some three
other variables were conceptualized to be determinants of the level of patient
satisfaction with outpatient healthcare services, namely;
4.5.1. Technical Quality and Provider Competence perspective
In order to assess patients’ perception of technical quality and healthcare provider
competence, a total of seven items were evaluated. These included attribute 1 (the
hospital has the resources needed to provide complete medical care), attribute 2
(hospital staff are qualified to serve adequately), attribute 3 (doctors and nurses give
me advice on ways to avoid illnesses), attribute 4 (generally, I waited for reasonable
time before being served), attribute 5 (doctors and nurses spent sufficient time with
me), attribute 6 (I received all drugs prescribed to me by the clinician) and attribute 7
(all the treatments/therapies recommended by the clinicians are available in the
facility). These items were subjected to hierachical regression to establish which items
best explained general satisfaction with outpatient healthcare services. Descriptive
statistics were run for all the items to assess for the accuracy of entry of data, mean
score for each item and normality. According to Table 4.51, high means above
average were recorded across all item measures with three items, attribute 3, attribute
4 and attribute 5 registering the lowest means.

39
Table 4.51 Descriptive Statistics for technical quality and provider competence
Attributes Mean Standard
De vi
ation
Skewness
Medical resources are available
Staff are qualified
Doctors and nurses give advice
Reasonable waiting t ime
Sufficient consultation time
Received all prescribed drugs
All t reatments/therapies available
4.36
4.69
3.35
3.47
3.93
4.37
4.00
.876
.594
1.632
1.334
1.158
1.226
1.451
-1.743
-2.033
-.352
-.393
-.952
-1.746
-1.074
The initial analysis focused on test for sampling adequacy using K.M.O’s test of
sampling adequacy and Bartlett’s test of sphericity for all attributes. The results
indicated that the sample size was adequate (KMO=0.728; χ2=634.089; df=21;
p<0.05).Further analysis was done to determine and extract factors that would explain
patients’ perceived technical quality and provider competence based on the seven
attributes. A total of seven factors were possible to be extracted but only two factors
met the criteria of eigen values set at one, namely technical quality 1 (TQ1) and
technical quality 2 (TQ2). The rest of the factors were not valid. Table 4.52 shows
that six out of the seven attributes emerged as measures of technical quality and
healthcare provider competence, accounting for 44.1% of the variance of technical
quality and provider competence. TQ1 which constituted items related to whether
doctors and nurses often gave advice on ways to avoid illnesses and stay healthy,
whether waiting time before service was reasonable, and whether service time was

40
sufficient, accounted for 30.64%. TQ2, which constituted items related to whether the
health facility had the resources needed to provide complete medical care, whether the
hospital staff were qualified to serve adequately, and whether respondents received all
the drugs prescribed by the clinicians, accounted for 13.46% of the variance.
Table 4.52 Rotated factor matrix for Technical quality and provider competence
Attributes
Factor
1
Factor
2
The hospital has the resources needed to provide complete medical care
Hospital staff are qualified to serve adequately
Doctors and nurses give me advice on ways to avoid illnesses
Generally, I waited for reasonable time before being served
Doctors and nurses spent sufficient time with me
I received all the drugs prescribed to me by the clin icians
All the treatments/therapies recommended by clinicians are available in the
facility
.699
.763
.594
.715
.556
.632
Overall variance explained was 44.1%
In order to show the distribution of factors, all the items were loaded into a rotated
factor space and displayed as shown in Figure 4.51. The idea of rotation is to reduce
the number of factors on which the variables under investigatio n have high loadings,
thereby making the analysis easier.
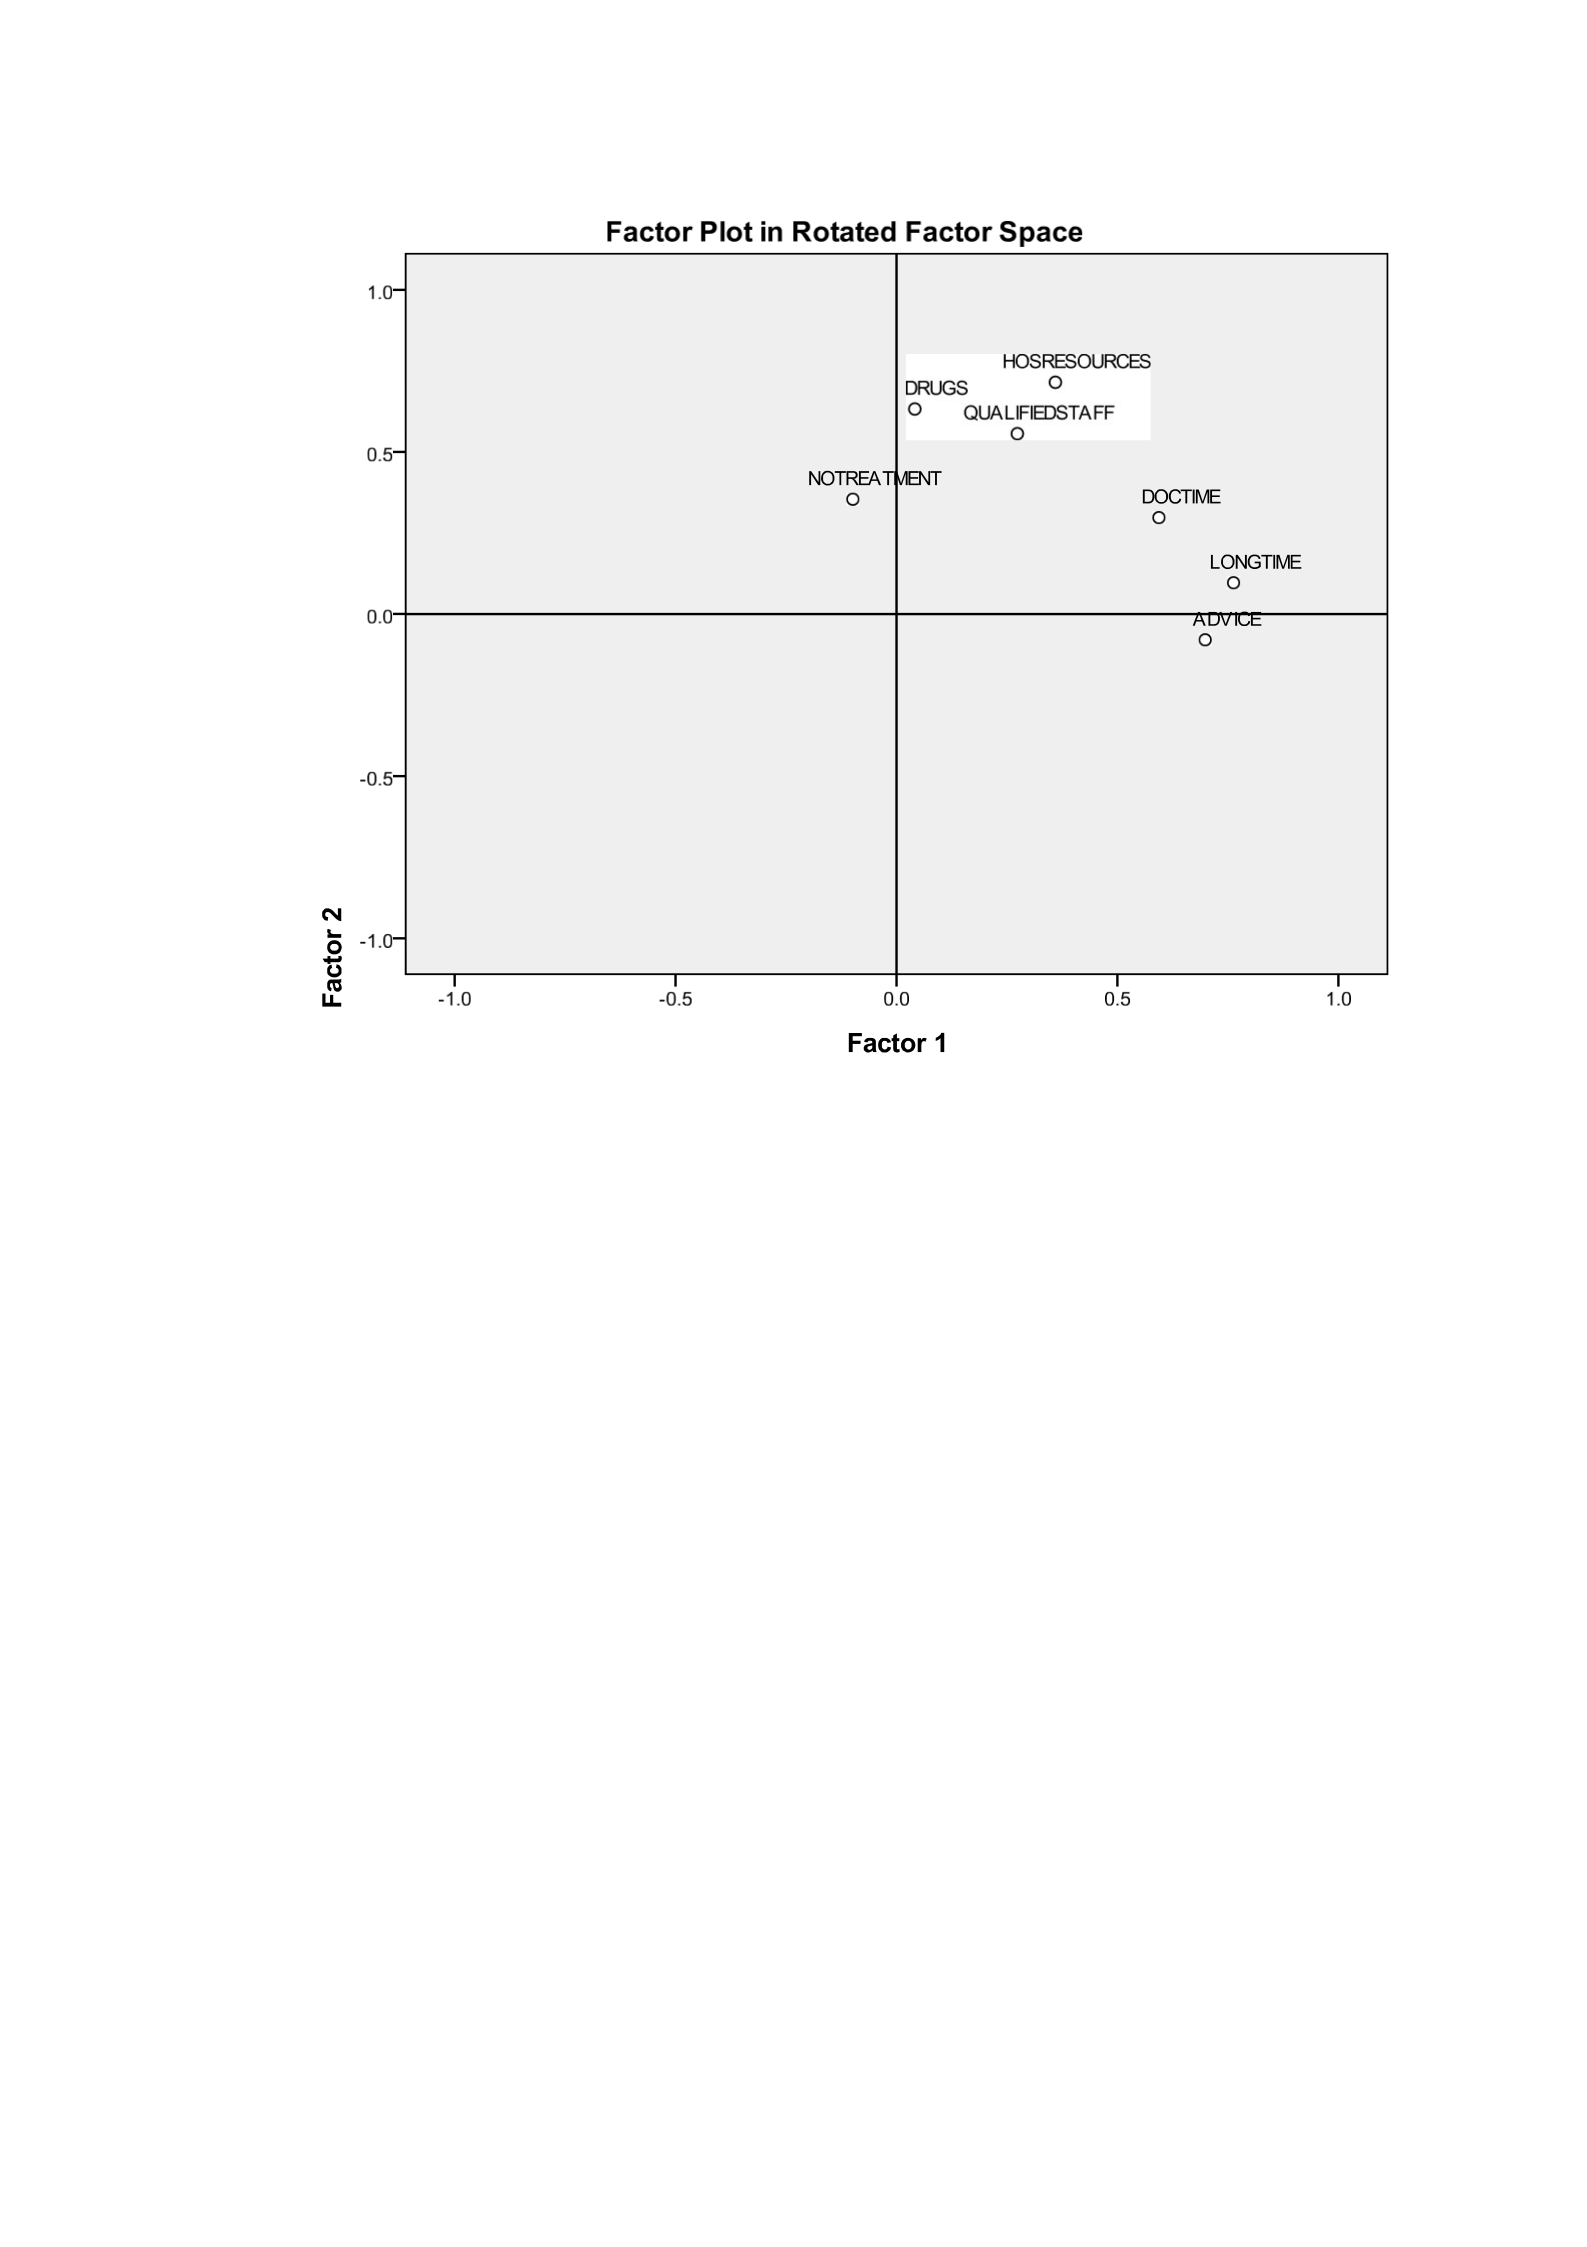
41
Figure 4.51: Factor plot in rotated factor space for technical quality and
provider competence
Finally each of the extracted factors were subjected to linear regression to determine
which of the attributes were the best significant predictors of technical quality and
provider competence. In this regard, analysis was done to show the magnitude of
predictors of Factor 1(TQ1). According to Table 4.53, the results indicated that three
items including giving advice on ways to avoid illnesses, waiting time before service
and time spent with the healthcare provider significantly explained up to 98.8% of
the total variance in patients’ perceived technical quality and provider competence
category-1 (R=0.988, F=5540.858, p<0.05). It emerged that reasonable waiting time
before service was the best predictor of patients’ perceived technical quality and
provider competence category- 1 (β=0.535, t=56.311, p<0.05). This was followed by

42
doctors and nurses giving advice on ways to avoid illnesses (β=0.467, t=51.187,
p<0.05) and finally spending sufficient time with the healthcare provider (β=0.197,
t=21.844, p<0.05).
Table 4.53 Regression Analysis of technical quality category - 1
Model Unstandardized
coefficients
Standardized
Coefficients
T
Sig.
B
Std.
Error
Beta
(Constant ) -3.500 .033 -106.118 0.000
Doctors and nurses give .332 .006 .467 51.187 0.000
advice
Waited for reasonable .465 .008 .535 56.311 0.000
time before service
Sufficient consultation .197 .009 .197 21.844 0.000
time
Analysis was also done to show the magnitude of predictors of Factor 2(TQ2). From
the results the three items including availability of resources in the hospital to offer
complete medical care, presence of qualified hospital staff and having received all
prescribed drugs significantly explained up to 92.7% of the total variance in patients’
perceived technical quality and provider competence category-2 (R=0.927,
F=801.499, p<0.05) as shown in Table 4.54. It was noted that having resources
necessary for complete medical care was the best predictor of patients’ perceived
technical quality and provider competence category- 2 (β=0.470, t=19.677, p<0.05).
This was followed by receiving all drugs prescribed by the clinicians (β=0.449,
t=20.935, p<0.05) and finally presence of qualified hospital staff (β=0.234, t=10.404,
p<0.05).

43
Table 4.54 Regression Analysis of Technical quality category - 2
Model
Unstandardized
coefficients
Standardized
Coefficients
T
Sig.
B
Std.
Error
Beta
(Constant ) -6.880 .181 -38.070 0.000
Resources for medical care .637 .032 .470 19.677 0.000
available
Hospital staff qualified
.469 .045 .234 10.404 0.000
Received all prescribed .436 .021 .449 20.935 0.000
drugs
4.5.2. Provider Interpersonal Aspects perspective
A total of eleven items were investigated to assess the respondents’ perception of the
healthcare provider’s interpersonal aspects. These items included attribute 1 (the
doctor who treated me has an interest in me as a person), attrib ute 2 (the hospital staff
are friendly), attribute 3 (the hospital staff treated me with respect), attribute 4, (the
hospital staff adhered to privacy and confidentiality while treating me), attribute 5
(during my visit I was allowed to say what I thought was important), attribute 6
(doctors were good in explaining the reasons for medical tests), attribute 7 (doctors
were good in explaining the diagnosis to me), attribute 8 (doctors used medical terms
and explained what they meant), attribute 9 (hospital staff always listened to me),
attribute 10 (I received explanation for any delay in getting a service) and attribute 11
(I was involved in making decisions concerning my treatment). These attributes were
subjected to hierarchical regression to establish whic h attributes best explained
patients’ perceived personal interpersonal aspects. Descriptive statistics were run for
all the items to assess for the accuracy of entry of data, mean score for each item
and

44
normality. Table 4.55 shows that means above average were recorded across all item
measures with two items, attribute 8 and attribute 10 registering the lowest means.
Table 4.55 Descriptive Statistics for provider interpersonal aspects
Attributes Mean Standard
De vi
ation
Skewness
Doctors concerned
Friendly hospital staff
Treated with respect by staff
Privacy and confidentiality
Allowed t ime to talk
Good e xp lanations for tests
Exp lanation of diagnosis ok
Exp lanation of medical terms
Being listened to by staff
Exp lanation for delayed service
Involvement in decision making
4.14
4.34
4.04
4.00
4.23
3.82
3.26
2.74
4.05
2.61
3.09
.974
.770
1.136
1.130
.923
1.179
1.470
1.572
.924
1.508
1.457
-1.283
-1.426
-1.331
-1.038
-1.137
-.646
-.250
.223
-.729
.325
-.318
The initial analysis focused on test for sampling adequacy using K.M.O’s test of
sampling adequacy and Bartlett’s test of sphericity for all attributes. The results
indicated that the sample size was adequate (KMO=0.824; χ2=1644.941; df=55;
p<0.05).Further analysis was done to determine and extract factors that would explain
patients’ perceived interpersonal aspects (interaction quality) based on the eleven
attributes. A total of eleven factors were possible to be extracted but only two factors
met the criteria of eigen values set at one, namely provider interpersonal aspects 1 (

45
PIA1) and provider interpersonal aspects 2 (PIA2). The rest of the factors were not
valid. According to Table 4.56, all the eleven attributes emerged as measures of
patients’ perceived interpersonal aspects, accounting for 48.47% of the variance of
interpersonal aspects. PIA1 which constituted items related to whether doctors were
concerned about their patients’ well being, whether the hospital staff were friendly,
whether respondents were treated with respect by hospital staff, whether hospital staff
adhered to privacy and confidentiality during treatment, whether respondents were
allowed to say everything they thought were important, whether doctors were good in
explaining the reasons for medical tests, and whether hospital staff always listened to
respondents, accounted for 30.42%. PIA2 which accounted for 18.05%, consisted of
four items related to whether doctors were good in explaining the diagnosis to
respondents, whether doctors used medical terms and explained what they meant,
whether respondents received any explanation for delayed service delivery, and
whether respondents were involved in making decisions concerning treatment.

46
Table 4.56 Provider interpersonal aspects Rotated Factor Matrix
Attributes
Factor
1
Factor
2
The doctor who treated me has an interest in me as a person
Hospital staff are friendly
The hospital staff treated me with respect
The hospital staff adhered to privacy and confidentiality while treating me
During my visit, I was allowed to say everything I thought was important
Doctors were good in e xp lain ing the reason for medical tests
Doctors were good in e xp lain ing the diagnosis to me
Doctors used medical terms and e xpla ined what they
meant Hospital staff always listen to me
I received e xplanation for any delays in getting a service
I was involved in making decisions concerning my treatment
.749
.786
.551
.568
.704
.562
.828
.617
.688
.760
.699
Overall variance explained was 48.47 %
In order to show the distribution of factors, all the items were loaded into a factor
space and displayed as shown in Figure 4.52.
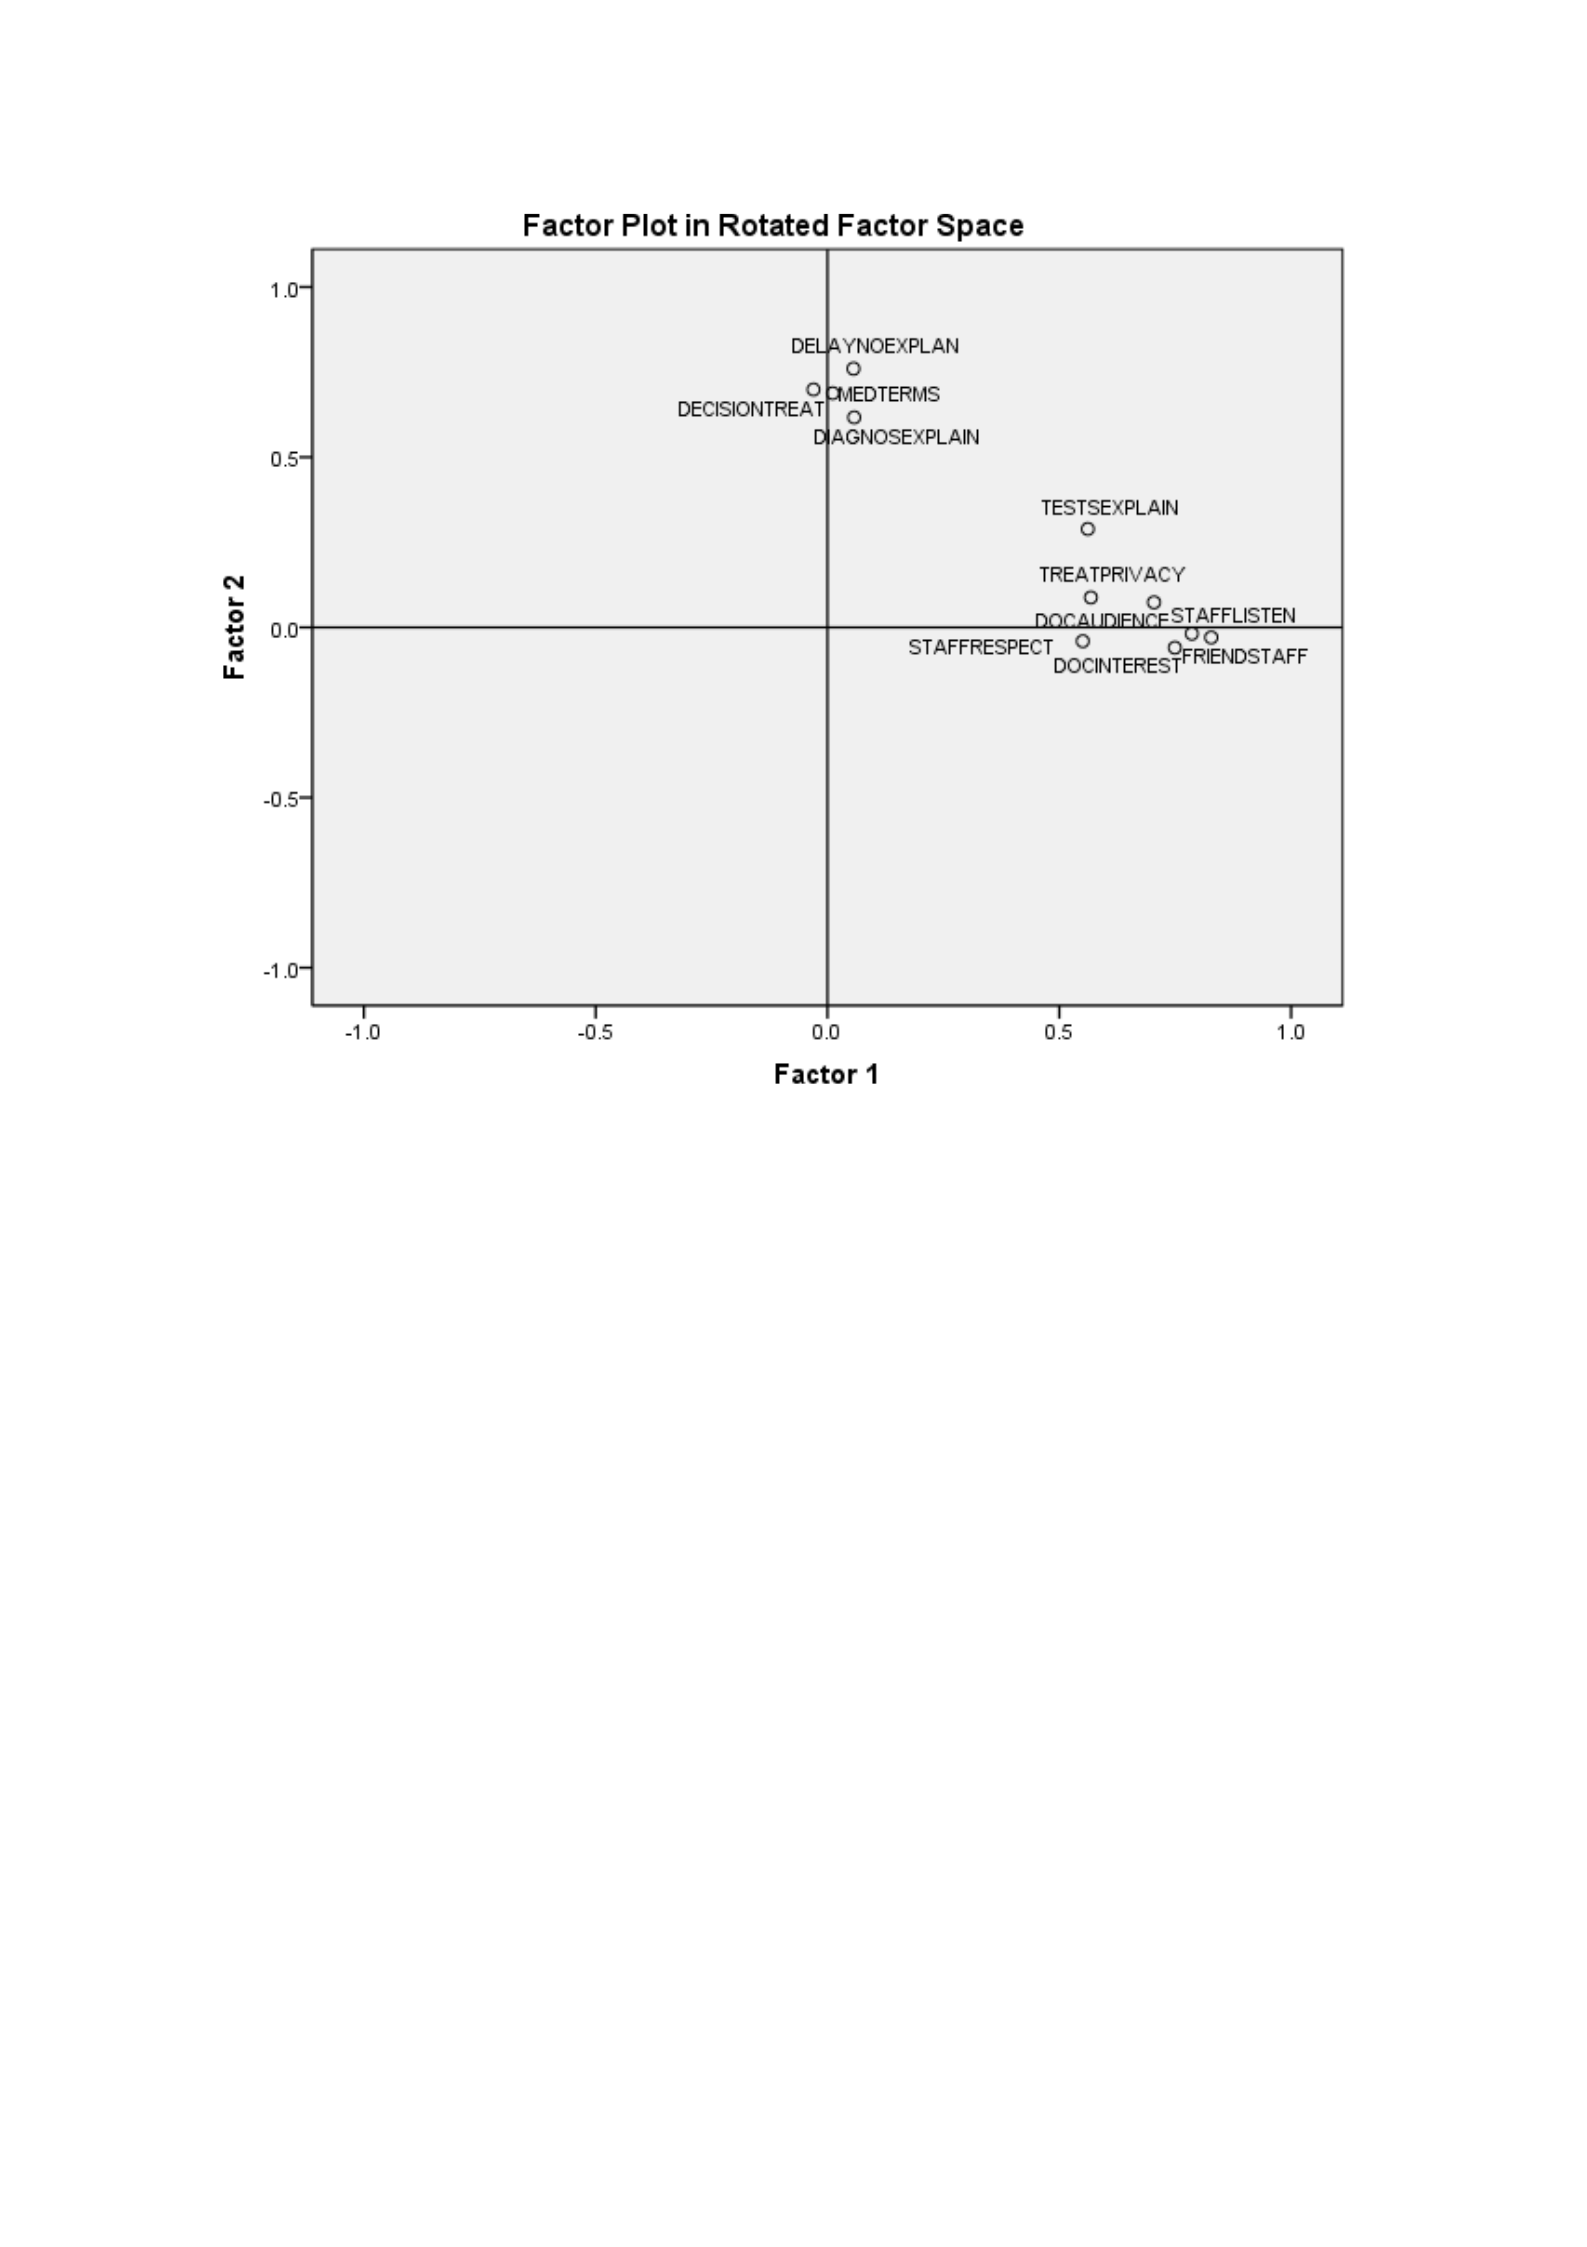
47
Figure 4.52: Factor plot in rotated factor space
Finally each of the extracted factors were subjected to linear regression to determine
which of the attributes were the best significant predictors of patients’ perceived
interpersonal aspects. In this regard, analysis was done to show the magnitude of
predictors of Factor 1(PIA1). Under PIA1, attribute 5 was dropped since it was
similar to attribute 9. The results indicated that six items significantly explained up to
99.1% of the total variance in patients’ perceived interpersonal aspects category-1
(R=0.991, F=3606.021, p<0.05) as shown in Table 4.57. It emerged that having
hospital staff listen to patients was the best predictor of patients’ perception of
interpersonal aspects category- 1 (β=0.380, t=37.037, p<0.05). This was followed by
friendly hospital staff (β=0.273, t=27.433, p<0.05), followed by doctors being
concerned about patients’ well being (β=0.251, t=25.689, p<0.05), then followed by
48
adherence to privacy and confidentiality during treatment (β=0.145, t=18.054,
p<0.05). This was followed by doctors being good at explaining reasons for various
medical tests (β=0.119, t=14.844, p<0.05) and lastly patients being treated with
respect by hospital staff (β=0.100, t=12.403, p<0.05).
Table 4.57 Regression Analysis of interpersonal aspects category - 1
Model
Unstandardized
coefficients
Standardized
Coefficients
T
Sig.
B
Std.
Error
Beta
(Constant ) -5.882 .043 -137.246 0.000
Attribute 1 .275 .011 .251 25.689 0.000
Attribute 2 .378 .014 .273 7.433 0.000
Attribute 3 .094 .008 .100 2.403 0.000
Attribute 4 .137 .008 .145 8.054 0.000
Attribute 6 .107 .007 .119 14.844 0.000
Attribute 9 .438 .012 .380 37.037 0.000
Similarly, regression analysis was done to show the magnitude of predictors of Factor
2(PIA2). From the results displayed in Table 4.58, four items significantly explained
up to 99.5% of the total variance in patients’ perception of interpersonal aspects
category-2 (R=0.995, F=8954.945, p<0.05). Receiving explanations for any delay in
getting a service was the best predictor of patients’ perception of interpersonal
aspects category- 2 (β=0.406, t=56.294, p<0.05). This was followed by involving
patients in decision making concerning their treatment (β=0.314, t=45.168, p<0.05),
followed by doctors using medical terms and explaining what they meant (β=0.307,

49
t=46.409, p<0.05 and finally doctors being good at explaining the diagnoses to their
patients (β=0.236, t=37.253, p<0.05).
Table 4.58 Regression Analysis of interpersonal aspects category - 2
Model
Unstandardized
coefficients
Standardized
Coefficients
T
Sig.
B
Std. Error Beta
(Constant ) -2.718 .017 -163.721 0.000
Attribute 7 .180 .005 .236 37.253 0.000
Attribute 8 .218 .005 .307 46.409 0.000
Attribute 10 .301 .005 .406 56.294 0.000
Attribute 11 .241 .005 .314 45.168 0.000
4.5.3. Hospital Milieu perspective
A total of nine items were investigated as measures of respondents’ perception of the
hospital milieu. These included attribute 1 (the hospital being conveniently located),
attribute 2 (being able to get medical aid whenever needed), attribute 3 (being able to
easily reach a doctor if one has a medical question), attribute 4 (being able to easily
access medical specialists in the hospital), attribute 5 (having to pay more than one
could afford for medical care), attribute 6 (the cost of healthcare services in this
facility), attribute 7 (proper maintenance of the health facility’s buildings), attribute 8
(cleanliness of the health facility) and finally attribute 9 (the physical appearance of
facilities in the hospital). Descriptive statistics were run for all the items to assess for
the accuracy of entry of data, mean score for each item and normality. Most attributes
recorded means above average except for attribute 5 and attribute 9 which registered
means below average as indicated in Table 4.59.

50
Table 4.59 Descriptive statistics for hospital milieu
Attributes Mean Standard
De vi
ation
Skewness
Hospital conveniently located
Able to get medical aid any time
Can easily reach a doctor
Easily access medical specialists
Paid more than could afford
Cost of healthcare reasonable
Proper maintenance of buildings
Cleanliness of health facility
Physical appearance of hospital
3.91
3.64
3.14
2.73
2.45
3.99
4.31
4.36
2.24
1.171
1.308
1.606
1.712
1.446
1.208
.721
.662
1.324
-.797
-.388
-.077
.269
.470
-.883
-.958
-.916
.881
The initial analysis focused on test for sampling adequacy using K.M.O’s test of
sampling adequacy and Bartlett’s test of sphericity for all attributes. The results
indicated that the sample size was adequate (KMO=0.817; χ2=2451.259; df=36;
p<0.05).Further analysis was done to determine and extract factors that would explain
patients’ perception of the hospital milieu based on the nine attributes. A total of nine
factors were possible to be extracted but only three factors met the criteria of eigen
values set at one, namely hospital milieu (HM1, HM2 and HM3). The rest of the
factors were not valid. All the nine attributes emerged as measures of patients’
perception of hospital milieu, accounting for 70.41% of the variance of hospital
milieu as shown in Table 4.510. HM1 which constituted items including the hospital
being conveniently located, ability to get medical aid whenever needed, ability to
easily reach a doctor when one has a medical question, ability to easily access medical
specialists in the hospital, cost of healthcare in the facility being reasonable and
finally appearance of the hospitals physical facilities, accounted for 49.23%. HM2

51
which accounted for 10.92% of the variance consisted of two items namely proper
maintenance of the health facility’s buildings and cleanliness of the health facility.
HM3 which accounted for 10.26% of the overall variance constituted two items
related to whether respondents had to pay more than they could afford for medical
care and whether the overall cost of healthcare services in the facility was reasonable.
Table 4.510 Hospital milieu Rotated Factor Matrix
Attributes
Factor
1
Factor
2
Factor
3
The hospital is conveniently located
I am able to get medical aid whenever I need it
If I have a medical question, I can reach a doctor for help without
any problem
I can easily access medical specialists in the hospital
I had to pay more than I could afford for medical care
Overall cost of healthcare in the facility is reasonable
The health facility’s buildings are well maintained
Generally, this health facility is clean
The facilit ies in this hospital are old fashioned
.703
.813
.830
.775
.411
.461
.835
.910
-.880
.575
Overall variance explained was 70.41%
In order to show the distribution of factors, all the items were loaded into a factor
space and displayed in Figure 4.53.
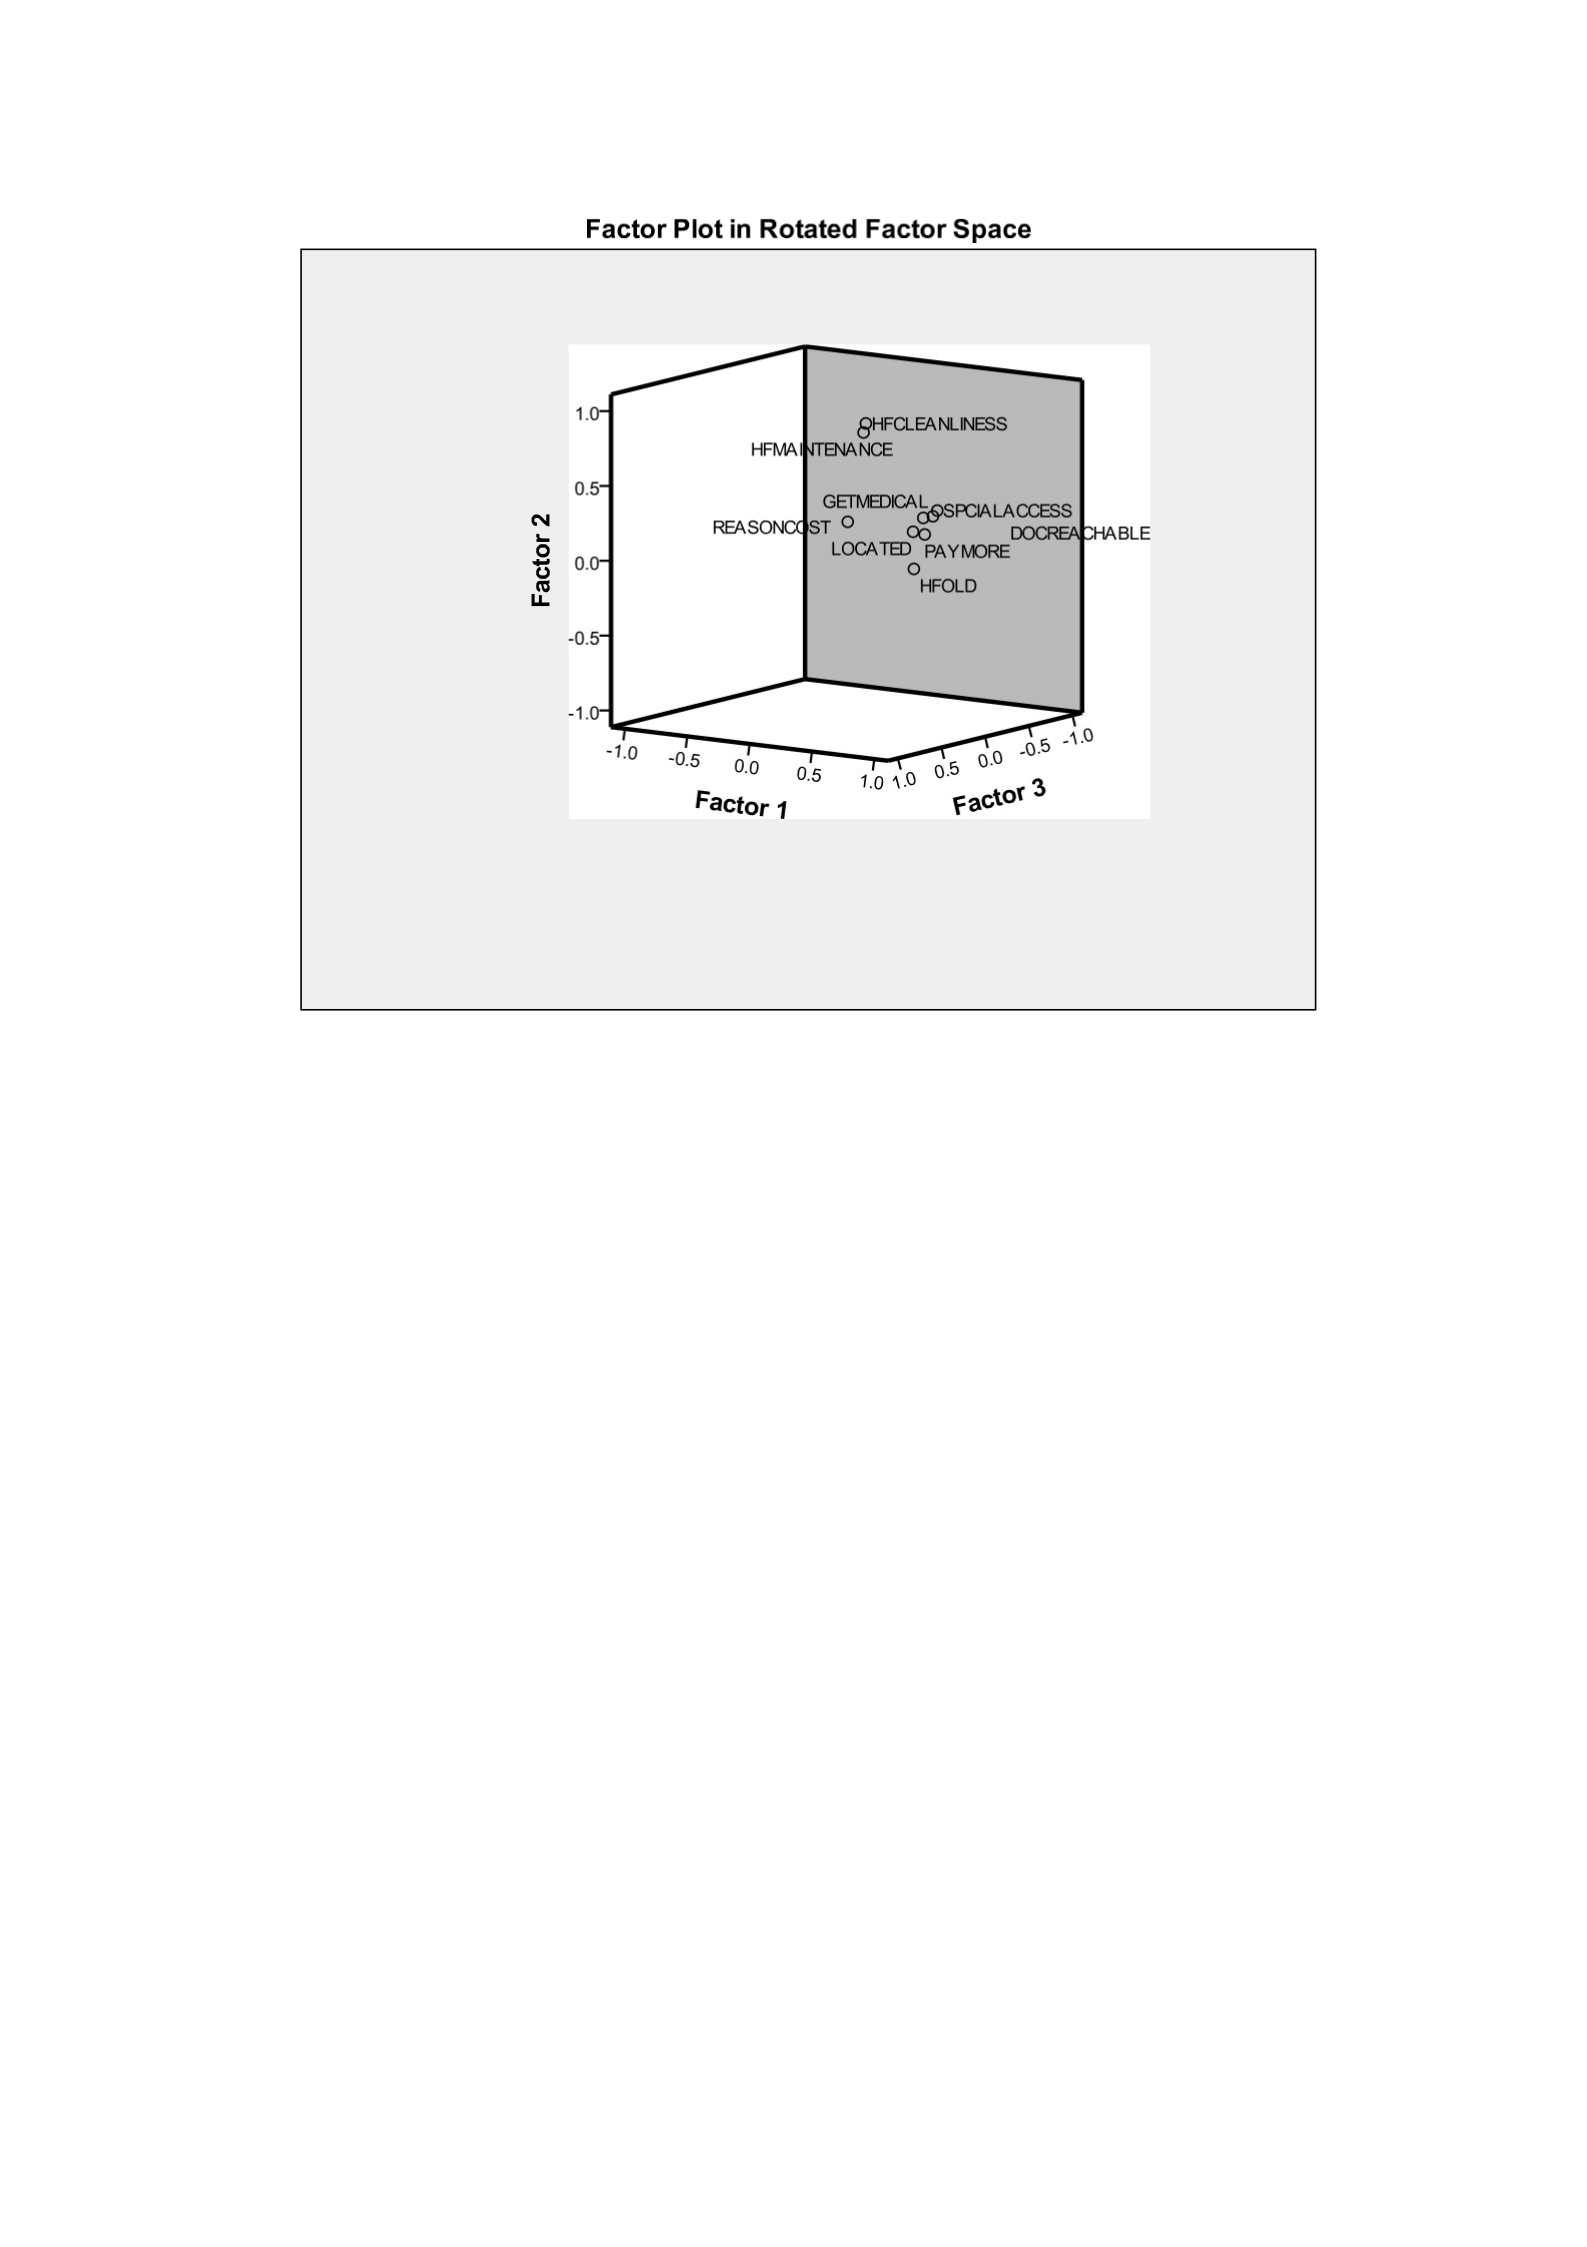
52
Figure 4.53: Factor plot in rotated factor space for hospital milieu
Eventually each of the extracted factors were subjected to linear regression to
determine which of the attributes were the best significant predictors of patients’
perception of hospital milieu. Analysis was therefore done to show the magnitude of
predictors of Factor 1(HM1). From the results displayed in Table 4.511, it emerged
that six items significantly explained up to 92.7% of the total variance in patients’
perception of the hospital milieu category-1 (R=0.927, F=395.925, p<0.05). An
attempt to establish the most powerful predictor of Factor 1 (HM1) revealed that being
able to reach a doctor when one has a medical question was the best predictor of
patients’ perception hospital milieu category- 1 (β=0.387, t=8.529, p<0.05). This was
followed by being able to get medical aid whenever needed (β=0.281, t=6.320,
p<0.05), followed by the cost of healthcare in the facility being reasonable (β= -0.236,

53
t= -9.716, p<0.05), then followed by the appearance of the hospital facilities
(β=0.209, t=10.290, p<0.05), then followed by the hospital being conveniently located
(β=0.190, t=5.800, p<0.05) and finally ability to easily access medical specialists in
the health facility (β=0.183, t=4.832, p<0.05).
Table 4.511 Regression Analysis of hospital milieu category - 1
Model
Unstandardized
coefficients
Standardized
Coefficients
T
Sig.
B
Std. Error Beta
(Constant ) -2.518 .086 -25.077 0.000
Attribute 1 .171 .030 .190 5.800 0.000
Attribute 2 .228 .036 .281 6.320 0.000
Attribute 3 .255 .030 .387 8.529 0.000
Attribute 4 .113 .023 .183 4.832 0.000
Attribute 6 -.207 .021 -.236 -9.716 0.000
Attribute 9 .167 .016 .209 10.290 0.000
Similarly, regression analysis was done to show the magnitude of predictors of Factor
2(HM2). From the results, two items significantly explained up to 96.5% of the total
variance in patients’ perception of hospital milieu category-2 (R=0.965, F=2635.838,
p<0.05) as shown in Table 4.512. Cleanliness of the health facility emerged as the
best predictor of patients’ perception of hospital milieu category-2 (β=0.698,
t=31.248, p<0.05). This was followed by proper maintenance of the health facility’s
buildings (β=0.309, t=13.831, p<0.05).
54
Table 4.512 Regression Analysis of hospital milieu category - 2
Model
Unstandardized
coefficients
Standardized
Coefficients
T
Sig.
B
Std.
Error
Beta
(Constant ) -6.833 .095 -71.799 0.000
Attribute 7 .454 .033 .309 13.831 0.000
Attribute 8 1.118 .036 .698 31.248 0.000
Finally, regression analysis was done to show the magnitude of predictors of Factor
3(HM3). From the results, two items significantly explained up to 98.9% of the total
variance in patients’ perception of hospital milieu category-3 (R=0.989, F=8620.335,
p<0.05), as shown in Table 4.513. Having to pay more than one could afford
emerged as the best predictor of patients’ perception of hospital milieu category-3
(β=
-0.898, t= -102.498, p<0.05). This was followed by the overall cost of healthcare
services being reasonable (β=0.160, t=18.245, p<0.05).
Table 4.513 Regression Analysis of hospital milieu category - 3
Model
Unstandardized
coefficients
Standardized
Coefficients
T
Sig.
B
Std. Error Beta
(Constant ) 1.106 .044 25.155 0.000
Attribute 5 -.692 .007 -.898 -102.498 0.000
Attribute 6 .147 .008 .160 18.245 0.000

55
4.6. Relationship among Socio-Demographic Factors, Patients’ Health
Characteristics, Perceived Technical Quality, Perceived Interaction Quality,
Perceived Hospital Milieu and General Outpatient Satisfaction
In order to address specific objective four which sought to determine the relationship
among factors associated with levels of patient satisfaction with outpatient care, a
simple regression analysis was performed. The aim was to determine the importance
of each element/variable in the factor structures. Regression coefficients, R square
value and model fit statistics were obtained for each factor in the three study
constructs. The results are presented in the sub-sections that follow.
4.6.1 Relationship between Socio-Demographic factors and overall Outpatient
satisfaction
Simple regression analysis was performed in order to determine the importance of
each element/variable in the factor structures as indicated in Tab les 4.61 and 4.62.
Table 4.61 Model summary for socio-demographics
Model
R
R S quare Adjusted R S quare
Std. Error of
the estimate
1
2
3
4
5
6
.132
a
.200
b
.209
c
.210
d
.227
f
.296
g
.017
.040
.044
.044
.052
.088
.015
.035
.036
.035
.040
.074
1.04126006
1.03046938
1.02991392
1.03082866
1.02813091
1.00977984

56
Table 4.62 ANOVA for socio-demographics
Model Sum of squares Df
Mean s quare.
F
Sig.
1
Regression
Residual
Total
Regression
Residual
Total
Regression
Residual
Total
Regression
Residual
Total
Regression
Residual
Total
Regression
Residual
Total
7.555
1
7.555 6.968 0.009
a
427.184 394 1.084
434.739 395
2
17.425
2
8.712 8.205 0.000
b
417.314 393 1.062
434.739 395
3
18.935
3
6.312 5.950 0.001
c
415.803 392 1.061
434.739 395
4
19.259
4
4.815 4.531 0.001
d
415.480 391 1.063
434.739 395
5
22.488
5
4.498 4.255 0.001
e
412.251 390 1.057
434.739 395
6
38.093
6
6.349 6.226 0.000
f
396.646 389 1.020
434.739 395

57
a. Predictors: (Constant), Gender
b. Predictors: (Constant), Gender, Age
c. Predictors: (Constant), Gender, Age, Highest Level of Education
d. Predictors: (Constant), Gender, Age, Highest Level of Education, Employment
Status
e. Predictors: (Constant), Gender, Age, Highest Level of Education, Employment
Status, Marital Status
f. Predictors: (Constant), Gender, Age, Highest Level of Education, Employment
Status, Marital Status, Place of residence
g. Dependent Variable: General outpatient satisfaction BART factor score
Tables 4.61 and 4.62 above, shows that gender of the respondent (G) could only
account for 1.7% (R2=0.017, F=6.968, p<0.05) of the variation in general outpatient
satisfaction. The difference between R2= 0.017 and adjusted R2=0.015 is 0.002 and
shows that the suggested model generalizes quite well as the adjusted R2 is too close
to R2. Shrinkage of less than 0.5 depicts that the validity of the model is very good
(Field, 2005). The other variations in general outpatient satisfaction i.e. 98.3% were
explained by other external factors outside the model. After addittion of the second
predictor, age of the respondent (A), the model explained 4.0% (R2=0.040, F=8.205,
p<0.05) of the variation in general outpatient satisfaction. The other variations in
general outpatient satisfaction i.e. 96.0% were explained by other external factors
outside the model. The difference between R2=0.040 and adjusted R2= .035 is 0.005,
again showing that the suggested second model can be used to generalize quite well
as the adjusted R2 is too close to R2. This further confirms the goodness of the

58
validity of the model as this shrinkage of 0.005 is well below the recommended
shrinkage cut off value of 0.5 by Field (2005). After inclusion of the third predictor
variable, highest level of education (HLE), the model explained 4.4 % (R2=0.044,
F=5.950, p<0.05) of the variation in general outpatient satisfaction. The difference
between R2 and adjusted R2 is 0.008 which was well below the recommended
shrinkage cut off value of 0.5. After the addition of the fourth predictor, employment
status (ES), the R2 value was still at 0.044 which explained 4.4% of the variation in
general outpatient satisfaction. The difference between R2 and the adjusted R2 is 0.009
and this was way below the recommended shrinkage cut off value of 0.5. Upon the
inclusion of the fifth predictor variable, marital status (MS), the model explained
5.2%(R2=0.052, F=4.255, p<0.05) of the variation in general outpatient satisfaction.
The other variations in general outpatient satisfaction i.e. 94.8% were explained by
other external factors outside the model. The difference between R2 and adjusted R2
was 0.012, again showing that the suggested fifth model can be used to generalize
quite well as the adjusted R2 is too close to R2. This further confirms the goodness of
the validity of the model as this shrinkage of 0.012 is well below the recommended
shrinkage cut off value of 0.5 by Field (2005). When the last predictor variable was
included, i.e. place of residence (POR), the model could explain 8.8%(R2= 0.088,
F=6.226, P<0.05) of the variation in general outpatient satisfaction. The other
variations in general outpatient satisfaction, i.e. 91.2% were explained by other
external factors outside this model. The difference between R2 and adjusted R2 was
0.014, suggesting that the sixth model can be used to generalize quite well as the
adjusted R2 is too close to R2. This again confirms the goodness of the validity of the
model as this shrinkage of 0.014 is well below the recommended shrinkage cut off
value of 0.5 by Field (2005).

59
Table 4.63: Regression Coefficients for the model for socio-demographics model
Model Un-
standardized
coefficients
Standardized
Coefficients
T
Sig.
B
Std. Error Beta
1
(Constant ) .449 .178 2.523 .012
Gender -.281 .107 -.132 -2.640 .009
2
(Constant) .156 .201 .775 .439
Gender -.258 .106 -.121 -2.443 .015
Age .111 .037 .151 3.049 .002
3
(Constant) -.003 .241 -.011 .991
Gender -.252 .106 -.118 -2.379 .018
Age .114 .037 .155 3.119 .002
Highest education .043 .036 .059 1.193 .233
4
(Constant) -.152 .362 -.420 .675
Gender -.256 .106 -.120 -2.408 .017
Age .117 .037 .158 3.162 .002
Highest education .058 .045 .080 1.286 .199
Employment status .033 .059 .034 .552 .581
5
(Constant) -.287 .369 -.776 .438
Gender -.252 .106 -.118 -2.377 .018
Age .131 .038 .178 3.473 .001
Highest education .038 .046 .053 .827 .409
Employment status .004 .061 .005 .072 .943
Marital status .175 .100 .093 1.748 .081
6
(Constant) .198 .383 .515 .607
Gender -.254 .104 -.119 -2.437 .015
Age .152 .037 .206 4.056 .000
Highest education .041 .045 .056 .893 .372
Employment status .002 .060 .002 .028 .978
Marital status .203 .099 .108 2.059 .040
Place of residence -.428 .109 -.192 -3.912 .000
The model (Table 4.63) suggests that all the variables except highest level of
education and employment status make a significant contribution to the model as they
have significant values of less than 0.05 and t-values greater than 0.893. The
regression equation can be written as follows
GOPS = 0.198-0.254G+1.52A+0.041HLE+0.002ES+0.203MS-0.428POR
Key:

60
GOPS- general outpatient satisfaction; G- gender; A- age; HLE- highest level of
education; ES- employment status; MS- marital status; POR- place of residence
4.6.2 Relationship between Patient’s Health Characteristics and General
Outpatient Satisfaction
A regression analysis was performed to test the degree to which general outpatient
satisfaction can be predicted by the three dimensions of patients’ health
characteristics. The regression analysis revealed an insignificant effect as shown in
Tables 4.64 and 4.65. All the three dimensions offered insignificant contributions.
Physical disability or not (PDN) dimension predicted 0.6%, nature of visit (NOV)
0.1% and condition treated for (CTF) 0.0%.
Table 4.64 Model summary for Regression model for patients’ health
characteristics
Model
R
R S quare Adjusted R S quare
Std. Error of
the estimate
1
2
3
.079
a
.084
b
.084
c
.006
.007
.007
.004
.002
-.001
1.04713514
1.04808977
1.04942209

61
Table 4.65 ANOVA for patients’ health characteristics
Model Sum of squares Df
Mean s quare.
F
Sig.
1
Regression 2.721
1
2.721 2.481 .116
a
Residual 432.018 394 1.096
Total 434.739 395
2
Regression 3.031
2
1.516 1.380 .253
b
Residual 431.707 393 1.098
Total 434.739 395
3
Regression 3.034
3
1.011 .918 .432
c
Residual 431.704 392 1.101
Total 434.739 395
a. Predictors: (Constant), Physically Disabled or Not
b. Predictors: (Constant), physically Disabled or Not, Nature of visit
c. Predictors: (Constant), physically Disabled or Not, Nature of visit, Condition
treated for
d. Dependent Variable: General outpatient satisfaction BART factor score
All the three patient health characteristics variables are all insignificant in predicting
general outpatient satisfaction as they all have significant values of more than 0.05 as
shown in Table 4.66. The regression equation can be written as follows;
GOPS= 0.686-0.300PDN-0.060NOV-0.005CTF
Key:
GOPS- general outpatient satisfaction; PDN- physically disabled or not; NOV- nature
of visit; CTF- condition treated for

62
Table 4.66: Regression coefficients for the model for patients’ health
characteristics model
Model
Unstandardized
coefficients
Standardized
Coefficients
T
Sig.
B
Std. Error Beta
1
(Constant ) .566 .363 1.559 .120
Disabled or not
-.296 .188 -.079 -1.575 .116
2
(Constant) .674 .416 1.619 .106
Disabled or not
-.299 .188 -.080 -1.591 .112
Nature of visit
-.060 .113 -.027 -.532 .595
3
(Constant) .686 .471 1.456 .146
Disabled or not
.300 .188 -.080 -1.590 .113
Nature of visit
-.060 .114 -.027 -.526 .599
Condition treated for -.005 .104 -.003 -.052 .958
4.6.5 Relationship between Service Quality Dimensions (i.e. Technical Quality
and Provider Competence, Provider Interpersonal Aspects, and Hospital Milieu)
and General Outpatient Satisfaction
Regression analysis done shows that Technical quality and provider competence
could account for 53.0% (R2=0.530, F=221.029, p<0.05) of the variation in general
outpatient satisfaction. The difference between R2 and adjusted R2 is 0.002 and shows
that the suggested model generalizes quite well as the adjusted R2 is too close to R2
(Tables 4.67 and 4.68)

63
Table 4.67: Model Summary for Regression Model for service quality
dimensions
Model
R
R S quare Adjusted R S quare
Std. Error of
the estimate
1
2
3
.728
a
.751
b
.762
c
.530
.564
.581
.528
.559
.574
.72113002
.69664358
.68515931
Table 4.68 ANOVA for service quality dimensions
Model Sum of squares Df Mean
square.
F
Sig.
1
Regression 229.883
2
114.942 221.029 .000
a
Residual 203.851 392 .520
Total 433.734 394
2
Regression 244.462
4
61.116 125.930 .000
b
Residual 189.272 390 .485
Total 433.734 394
3
Regression 252.060
7
36.009 76.705 .000
c
Residual 181.675 387 .469
Total 433.734 394
a. Predictors: (Constant), Technical quality and provider competence 2 BART factor score, Technical
quality and provider competence BART factor score
b. Predictors: (Constant), Technical quality and provider competence 2 BART factor score, Technical
quality and provider competence BART factor score, Provider interpersonal aspects 2 BART factor
score, Provider interpersonal aspects BART factor score

64
c. Predictors: (Constant), Technical quality and provider competence 2 BART factor score, Technical
quality and provider competence BART factor score, Provider interpersonal aspects 2 BART factor
score, Provider interpersonal aspects BART factor score, Hospital milieu 3 BART factor score ,
Hospital milieu BART factor score, Hospital milieu 2 BART factor score
d. Dependent Variable: General outpatient satisfaction BART factor score
Shrinkage of less than 0.5 depicts that the validity of the model is very good (Field,
2005). The other variations in general outpatient satisfaction i.e. 47.0% were
explained by other external factors outside the model. After the addition of the second
predictor variable, i.e. Provider interpersonal aspects, the model could account for
55.9% (R2=0.559, F=125.930, p<0.05) of the variation in general outpatient
satisfaction. The difference between R2 and adjusted R2 is 0.005 and again this shows
that the suggested model generalizes quite well as the adjusted R2 is too close to R2.
Shrinkage of less than 0.5 depicts that the validity of the model is very good (Field,
2005). The other variations in outpatient loyalty i.e. 46.1% were explained by other
external factors outside the model. The addition of the third predictor under service
quality, i.e. hospital milieu, saw the model account for 58.1% (R2= .581, F=76.705,
p<0.05) of the variation in general outpatient satisfaction. The difference between R2
and adjusted R2 is 0.007, indicating that the suggested model generalizes quite well as
the adjusted R2 is too close to R2. The regression model indicates that all the variables
except PIA2 and HM2 are significant in predicting general outpatient as they have
significant values of less than 0.05 with t-values greater than 1.289 as shown in
Table
4.69. The regression equation can be written as follows;
GOPS=-

65
0.001+0.352TQ1+0.258TQ2+0.198PIA1+0.018PIA2+0.144HM1+0.060HM2+0.11
3HM3
66
Key:
GOPS-general outpatient satisfaction; TQ- technical quality; PIA- provider
interpersonal aspects; HM- hospital milieu
Table 4.69: Regression coefficients for service quality dimensions model
Model Unstandardized
coefficients
Standardized
Coefficients
T
Sig.
B
Std. Error Beta
1
(Constant ) -.001 .036 -.031 .975
TQ1 .576 .032 .638 18.301 .000
TQ2 .381 .031 .432 12.387 .000
2
(Constant) -.002 .035 -.045 .964
TQ1 .432 .042 .478 10.364 .000
TQ2 .258 .038 .292 6.864 .000
PIA1 .267 .049 .271 5.468 .000
PIA2 .006 .034 .006 .181 .857
3
(Constant) -.001 .034 -.027 .978
TQ1 .352 .046 .390 7.638 .000
TQ2 .258 .040 .292 6.393 .000
PIA1 .198 .055 .201 3.596 .000
PIA2 .018 .037 .019 .500 .617
HM1 .144 .046 .146 3.156 .002
HM2 .060 .047 .061 1.289 .198
HM3 .113 .036 .120 3.154 .002

67
CHAPTER FIVE: DISCUSSION OF RESULTS
5.1. Introduction
This chapter presents a detailed discussion of the study findings, as per the research
objectives.
5.2. Discussion of Research Findings
The first objective of the study was to assess patients’ perceived importance of
healthcare service attributes. Out of the twelve healthcare service attributes
investigated, eleven emerged as key measures of importance of healthcare service
delivery attributes. These included friendliness of hospital staff, knowledge and
competence of staff, treating patients with respect, cleanliness and tidiness of the
health facility, overall appearance of the staff, guidance and information provided on
patients’ health needs, cost of healthcare, privacy and confidentiality, accessibility
and availability of healthcare, waiting time before service and time spent with the
healthcare provider. It was also noted that all the eleven item measures extracted were
significant. The findings revealed that being treated with respect by the hospital staff,
presence of friendly and competent staff and cleanliness of hospitals were the best
predictors of importance of healthcare service attributes. These findings support other
researchers’ findings that kindness of nurses and physicians, communicating with
patients and offering individualized care among others, are important healthcare
service attributes (Schoenfelder et al., 2011; Tung and Chang 2009; Sekandi et al.,
2011). Accessibility and availability of healthcare, provision of health education,
waiting time, cost of healthcare, service time and finally adherence to privacy and
confidentiality during treatment was the second most important predictor-category of
patient perceived importance of healthcare service attributes.

68
The second objective of this study was to determine the level of patients’ satisfaction
with outpatient healthcare services at Busia district hospital. The perceived level of
patient satisfaction with outpatient services in the health facility was measured as an
outcome variable. Four items were investigated in order to assess the level of overall
satisfaction with outpatient healthcare services offered at Busia district hospital. Item
number 3 was however dropped since it was similar to item 1. There was significant
difference for all the three items extracted as key measures of general satisfactio n
with outpatient healthcare services between the respondents who were satisfied and
those who were dissatisfied. The study assumed that the expected level of satisfaction
with outpatient services was at 50% in the study population. Further analysis
indicated that there was significant difference between the expected level of
satisfaction and the observed level of satisfaction for all the three attributes. This
implies a much higher level of satisfaction with outpatient healthcare services at Busia
district hospital than expected. This is in agreement with several studies, (
Schoenfelder et al., 2011, Meredith et al., 2008, Muhondwa et al., 2008 and Birhanu
et al., 2010), that most patients report satisfaction with the care they receive both in
public and private hospitals.
The third study objective was to identify factors associated with satisfaction with
outpatient healthcare services at Busia district hospital. Besides socio-demographic
factors and patients’ health characteristics, some three other variables, namely;
patient-perceived technical quality and provider competence, provider interpersonal
aspects and hospital milieu were conceptualized to be determinants of patient
satisfaction with outpatient healthcare services. The results of the study suggested that
most factors measured had a significant impact on general outpatient satisfaction

69
although not all the sub- factors made a significant contribution. Socio-demographic
factors accounted for 8.8% of the variation in general outpatient satisfaction
Furthermore, age of the respondents emerged as the most important predictor of
general outpatient satisfaction since it had the highest beta value. Place of residence of
the respondents was the second most important predictor followed by gender and
finally, marital status. These findings are in line with those of other researchers that
socio-demographic factors are important determinants of patient satisfaction (Zwier
and Clarke 2001; Myburgh et al., 2005 and Levinton et al., 2011). Highest level of
education and employment status did not make a significant contribution in
determining general outpatient satisfaction since the two had significant values of
more than 0.05. Patients’ health characteristics accounted for only 0.7% of the
variation in general outpatient satisfaction. All the sub-dimensions namely; physically
disabled or not, nature of visit and condition treated for did not make significant
contribution in predicting general outpatient satisfaction since they all had significant
values of more than 0.05. These findings are in contrast with the opinions of other
researchers that nature of hospital visit, illness treated and the physical health status of
patients are critical determinants of patient satisfaction (Sekandi et al., 2011 and Da
Costa et al., 1990).
Overall, service quality dimensions accounted for 58.1% of the variation in general
outpatient satisfaction, with technical quality and provider competence accounting for
53%, interpersonal aspects 6.9% and hospital milieu 2.2%. For technical quality, out
of the seven item measures evaluated, six emerged as key measures of patients’
perception of technical quality and healthcare provider competence, accounting for

70
44.1% of total variability. It was also noted that all the six item measures extracted
were significant. The findings revealed that reasonable waiting time before service,
patient health education and spending sufficient time with the healthcare service
provider were the best predictors of patient perceived technical quality. It is thought
that through health education, patients get an improved understanding of various
medical conditions, their diagnosis, management and ways of preventing them. It
could also be that patients feel that the health care provider has provided the
information that they need and this may lead them to more effective use of medical
services. Patients come to health care institutions with different health problems and
they seek remedy for their problems. This puts them in need to be well heard whilst
they are talking about their problems. To have adequate consultation duration may
allow health care providers to do so and know about their client and their health
problems for consequent decision and effective consultation. In order to make the
services easy to get by the patients, health care providers may hurry to the next case
without giving enough consultation time for the patients at hand. However, this
fashion of addressing the problem of the service has its own impact on the receiver of
the services and causes dissatisfaction. It is therefore important for the healthcare
provider to balance between consultation time and waiting time. More-over, hurry
may undermine health care providers’ empathy, perceived technical competency and
other important characteristics of the services. Availability of adequate resources in
the health facility, presence of qualified healthcare service providers and availability
of prescribed drugs emerged as the second most important predictor-category of
patient perceived technical quality. This could be because patients come to health care
institutions with different health problems and they seek remedy for their problems. It
is therefore important to them that they should be handled by the r ight personnel who

71
have the relevant skills to solve their problems. The effect of qualified healthcare
providers can only be felt by their clients if the prescribed modes of treatment
especially medicines are available.
For provider interpersonal aspects, all the eleven item measures evaluated emerged as
key measures of patients’ perception of interaction quality, accounting for 48.4% of
total variability. It was also noted that all the eleven item measures extracted were
significant. The findings revealed that being allowed to speak about their illnesses
was the best predictor of patient perceived interaction quality. Other important
predictors in this first category included friendly hospital staff, doctors being
concerned about their patients’ well being, adherence to privacy and confidentiality
during treatment, good explanations on the reasons for medical tests, and being
respected by hospital staff. There are a lot of interactions between patients and
healthcare service providers during the process of service delivery. Patients have
special characteristics, which makes them differ from a regular customer who wants
to receive a service. They are not in their best physical or mental condition, making
communication with this type of customer unique. It is thought that patients would be
more willing to open up to health service providers who are concerned about their
well being, are respectful and are friendly. More-over, being allowed to talk about
your ailment puts the client at ease with the health service provider, and this may
result in optimal utilization of healthcare services. Observing privacy and
confidentiality could be important since it fulfills patients’ sense of dignity and honor.
Item measures in the second category included receiving explanations for delayed
services, patients’ involvement in decision making concerning their treatment, doctors

72
using and explaining meanings of medical terms and finally, good explanation of the
diagnoses.
Under hospital milieu, all the nine item measures evaluated emerged as key measures
of patients’ perception of the hospital milieu, accounting for 70.41% of total
variability. It was also noted that all the nine item measures extracted were
significant. Items related to accessibility, affordability, convenience and availability
of healthcare services emerged as the most important predictors of patient perception
of hospital milieu These findings on service quality sub-dimensions support several
researchers’ opinions that service quality is a predictor of patient satisfaction
(Schoenfelder et al., 2011; Tung and Hang, 2009 and Sekandi et al., 2011).
Patient loyalty and recommendation of services to others was thought to be a resultant
of patient satisfaction. The results showed that general outpatient satisfaction
accounted for 20.9% of the variation in patient loyalty and recommendation of service
to others. General outpatient satisfaction proved to be a significant predictor of patient
loyalty and recommendation of service to others since it had a significant value of less
than 0.05. This finding is in agreement with the opinions of other researchers that
overall patient satisfaction is an important determinant of patient loyalty are positively
correlated (Mortazavi et al., 2009)
The final objective of this study was to determine the relationship between factors
associated with patient satisfaction with outpatient healthcare services and the level of
outpatient satisfaction. The conceptual model developed by the researcher postulated
that “individual determinants” and ‘‘service quality determinants’’ directly impacts
on

73
“outpatient satisfaction” which in turn impacts directly on “patient loyalty and
recommendation of service to others”. Results from the model tests indicated that
there is both negative and positive influence of socio-demographic factors and service
quality sub-dimensions on general outpatient satisfaction. The socio-demographic
sub-dimensions of age, marital status, highest level of education and employment
status showed a positive influence, while gender and place of residence revealed a
negative influence on general outpatient satisfaction. Even though some researchers
have not found any correlation between gender and patient satisfaction indices
(Rahmqvist, 2001), the findings of the current research are in line with those of other
researchers that socio-demographic factors, including gender, are important
determinants of patient satisfaction (Zwier and Clarke 2001; Myburgh et al., 2005;
Levinton et al., 2011). All the sub-dimensions of patient health characteristics
revealed a negative influence on general outpatient satisfaction, but none emerged as
a key determinant of general outpatient satisfaction. Similarly, all the sub-dimensions
of service quality revealed a positive influence on general outpatient satisfaction.
These findings support several researchers’ opinions that service quality is a predictor
of patient satisfaction and has a positive correlation (Schoenfelder et al., 2011; Tung
and Chang 2009 and Sekandi et al., 2011). Relationship between general outpatient
satisfaction and customer loyalty and recommendation of service to others was also
investigated, with the results indicating a positive relationship between the two
constructs. This finding also support the opinions of other researchers that overall
patient satisfaction and loyalty are positively correlated (Mortazavi et al., 2009)

74
CHAPTER SIX: SUMMARY, CONCLUSIONS AND RECOMMENDATIONS
6.1. Summary
This study sought to identify the determinants of patient satisfaction with outpatient
healthcare services at Busia district hospital, which may be useful in evaluating
service quality. The dimensions explored proved to be applicable in this setting.
6.2. Conclusions
The patients’ perceived importance of healthcare service attributes was investigated.
The study findings revealed that being treated with respect by the hospital staff,
presence of friendly and competent staff and cleanliness of hospitals were the most
important healthcare service attributes. Other important attributes included
accessibility and availability of healthcare, provision of health education, reasonable
waiting time, cost of healthcare, adequate consultation time and finally adherence to
privacy and confidentiality during treatment
The perceived level of patients’ satisfaction with outpatient healthcare services at
Busia district hospital was measured as an outcome variable. This study found that
there was significant difference between the expected level of satisfaction and the
observed level of satisfaction for all the three attributes under investigation. This
implies a much higher level of satisfaction with outpatient healthcare services at Busia
district hospital than expected.

75
The third study objective was to identify factors associated with satisfaction with
outpatient healthcare services at Busia district hospital. This study established that
technical quality attributes including provision of health education to clients,
perceived adequacy of consultation time and perceived reasonable waiting time were
the most important determinants of patient satisfaction with outpatient healthcare
services. The presence of qualified healthcare providers and availability of essential
resources especially prescribed drugs also proved to be important in patients’
evaluation of healthcare service quality. Interaction quality attributes including
effective communication between hospital staff and the patients as well as perceived
doctors’ concern about their patients’ well being, friendliness of hospital staff, being
treated with respect by hospital staff, adherence by hospital staff to privacy and
confidentiality during treatment emerged as important predictors of general outpatient
satisfaction. Accessibility, availability, affordability and convenience of healthcare
services also emerged as strong determinants of outpatient satisfaction. Cleanliness of
the health facility and proper maintenance of its physical facilities are also important
determinants of outpatient satisfaction. Armed with a good understanding on the
factors that patients use to evaluate overall service quality, healthcare providers will
be in a better position to enhancing the former’s satisfaction. Patient satisfaction and
positive evaluation of overall service quality leads to building a loyal client base.
The final objective of this study was to determine the relationship between factors
associated with patient satisfaction with outpatient healthcare services and the level of
outpatient satisfaction. The socio-demographic sub-dimensions of age, marital status,
highest level of education and employment status showed a positive correlation,

76
while

77
gender and place of residence revealed a negative correlation with outpatient
satisfaction. All the sub-dimensions of patient health characteristics had a negative
correlation with outpatient satisfaction, but none emerged as a key determinant of
general outpatient satisfaction. Similarly, all the sub-dimensions of service quality
revealed a positive correlation with general outpatient satisfaction.
6.3. Recommendations
Based on this study’s results, the following recommendations regarding satisfaction
with outpatient healthcare services at Busia district hospital are suggested:
i. There is need for the management of Busia district hospital to ensure that
healthcare providers offer adequate and regular health education and advice to
their clients.
ii. There is need for healthcare service providers to strike a balance between
consultation time and waiting time.
iii. The management of Busia district hospital should ensure that only qualified
staff provides services and that the essential medical supplies are available.
The hospital, in devising its long-term strategy should pay sufficient attention
to the development of its human resources. Such a strategy should be
leveraged on attracting and retaining competent and customer-oriented
medical and administrative staff, investing in continuous professional
development of staff and using advanced technologies to improve the quality
and speed of customer services.
iv. There is need to ensure that the health facility is easily accessible to clients
and that the layout is customer friendly. In addition, they should ensure that

78
the charges are reasonably affordable and that doctors, including medical
specialists, are easily reachable.
6.4. Recommendations for Further Research
Further studies should be considered on how a deliberate monitoring of overall quality
improvement in health facilities might contribute to quality of care and client
satisfaction.

79
REFERENCE
1. Abraham, K. G., Maitland, A., and Bianchi, S., (2006): Non-response in the
American time use survey. Public Opinion Quarterly. 70(5):676-703.
2. Ahmad, N. Z., Byrnes, G., Naqvi, S. A. (2008): A meta-analysis of ambulatory
versus inpatient laparoscopic cholecystectomy. Endoscopic Surgery. 22:1928–
1934.
3. Andaleeb, S.S., Siddiqui, N. and Khandakar, S. (2007): Patient satisfaction with
health services in Bangladesh. Health policy plan. 22:263-273.
4. Anderson, R.T., Camacho, F.T. and Balkrishnan, R. (2007): Willing to wait?:
The influence of patient wait time on satisfaction with primary care. Biomedical
Central Health Services Research. 7: 31.
5. Ben-Sira, Z. (1976): The function of the professional’s affective behavior in
client satisfaction: a revised approach to social interaction theory. Journal of
Health and Social Behavior. 17: 3-11.
6. Bielen, F. and Demoulin, N. (2007): Waiting time influence on satisfaction-
loyalty relationship in services. Managing service quality. 17(2): 174-193.
7. Birhanu, Z., Assefa, T., Woldie, M. and Morankar, S. (2010): Determinants of
satisfaction with healthcare provider interactions at health centers in Central
Ethiopia: a cross sectional study. Biomedical Central Health Services Research.
10:78.

80
8. Boyer, L., Francois, P. and Doutre, E. (2006): Perception and use of the results
of patient satisfaction surveys by care providers in a French teaching hospital.
International Journal for Quality Health Care. 18: 359-364.
9. Calnan, M. (1988): Towards a conceptual framework of lay evaluation of health
care. Social Science Medicine. 27:927–33.
10. Chakraborty, G., Gaeth, G.J. and Cunningham, M. (1993): Understanding
consumers' preferences for dental service. Journal of Health Care Marketing.
13(3):48-58.
11. Cleary, P.D., Edgman-Levitan, S. (1997): Health Care Quality Incorporating
Consumer Perspectives. Journal of America Medical Association. 278 (19):
1608 - 1612
12. Cleary, P.D. and McNeil, B.J. (1988): Patient satisfaction as an indicator of
quality care. Inquiry.25:25–36.
13. Coulter, A. (2006): Can patients assess the quality of health care? British
Medical Journal. 333:1-2.
14. Crow, R., Gage, H. and Hampson, S. (2002): The measurement of satisfaction
with healthcare: implications for practice from a systematic review of the
literature. Health technology assessment. 6:1-244.
15. Da Costa, D., Clarke, A. and Dobkin, P. (1999): the relationship between health
status, social support and satisfaction with medical care among patients with
systemic lupus erythematosus. International Journal for Quality in Healthcare.
11: 201-207.
16. Dagger, T.S., Sweeny, J.C., and Johnson, L.W. (2007): A hierarchical model of
health service quality: scale development and investigation of an integrated
model. Journal of Service Research. 10(2): 123-142

81
17. Donabedian, A. (1988): The quality of care: how can it be assessed?
Journal of America Medical Association.260:1743–8.
18. Dunlop, L., Umstad, M., Mcgrath, G., Reidy, K. and Brennecke, S. (2003): Cost
effectiveness and patient satisfaction with pregnancy day care for hypertensive
disorders of pregnancy. Australian and New Zealand Journal of Obstetrics and
Gynaecology. 43: 207–212.
19. Field, A. (2005): Discovering Statistics using SPSS.
20. Fisher, R.A. (1950): statistical methods for research workers. London: Oliver
and Boyd. 11thedition.
21. Gotlieb JB: Understanding the effects of nurses, patients' hospital rooms, and
patients' perception of control on the perceived quality of a hospital. Health
Marketing Quarterly. 18(1–2):1-14
22. Grogan, S., Conner, M. and Norman, P. (2000): Validation of a Questionnaire
measuring patient satisfaction with general practitioner services. Journal for
Quality Health Care. 9: 210-215.
23. Guldvog, B. (1999): Can patient satisfaction improve health among patients with
angina pectoris? International Journal for Quality in Health Care. 11: 233-240.
24. Hall, J.A. and Dornan, M.C. (1990): Patients’ demographic characteristics as
predictors of satisfaction with medical care: a meta-analysis. Social science and
medicine. 30: 811-818.
25. Hopkins, A., Gabbay, J., Neuberger, J. (1994): Role of users of health care in
achieving a quality Service. Quality in Health Care. 3:203-209.
26. Hornsby, A. S. and Crouther, J. (2000): Oxford advanced learners’ dictionary.
Oxford University Press. 1042.

82
27. Iezzoni, L.I., Davis, R.B., Soukup, J. and O’day, B. (2002): Satisfaction with
quality and access to healthcare among people with disabling conditions.
International Journal for Quality in Healthcare. 14(5): 369-381.
28. Isatou, K.J., Yiing- Jeng, C., Tsai- Ling, L. and Huang, N. (2012): Women’s
perception of antenatal care services in public and private in the Gambia.
International Journal for Quality Health Care. 24(6): 595-600.
29. Jitta, J., Arube, W.J. and Munyinda, H. (2008): Study of client satisfaction with
health services in Uganda. Child Health and Development Center, Makerere
University Medical School.
30. Kols, J.A. and Sherman, J.E. (1998): Family Planning Programs: Improving
Quality. Population Reports.
31. Lantz, P.M., Janz, N.K., Fagerlin, A., Schwartz, K., Liu, L., Lakhani, I., Salem,
B. and Katz, S.J. (2005): Satisfaction with Surgery Outcomes and the Decision
Process in a Population-Based Sample of Women with Breast Cancer. Health
Services Research. 40 (3): 745 – 767.
32. Levinton, C., Veillard, J., Slutsky, A. and Brown, A. (2011): The importance of
place of residence in patient satisfaction. International Journal for Quality in
Healthcare. 23(5): 495-502.
33. Marchisio, S., Ferraccioli, K., Barbieri, A., Porcelli, A. and Panella, M. (2006):
Care pathways in obstetrics: the effectiveness in reducing the incidence of
episiotomy in childbirth. Journal of Nursing Management. 14: 538–543.
34. Marcinowiz, L., Chlabicz, S. and Grebowsk, R. (2009): Patient satisfaction with
healthcare provided family doctors: primary dimensions and an attempt at
typology. Biomedical Central Health Services Research. 9: 63.

83
35. Marley, K.A., Collier, D.A. and Goldstein, S.M. (2004): The role of clinical and
process quality in achieving patient satisfaction in hospitals. Decision Sciences.
35(3): 349-369.
36. Meredith, P.H., Peters, D.H., Viswanathan, K., Rao, K.D., Mashkoor, A. and
Burnham, G. (2008): Client perceptions of the quality of primary care services in
Afghanistan. International Journal for Quality in Healthcare. 6: 384-391.
37. Ministry of Medical Services (2008). Strategic plan 2008-2012
38. Ministry of Medical Services and Ministry of Public Health and Sanitation
(2011): Comprehensive National Health Policy Framework 2011-2030.
39. Ministry of Medical Services and Ministry of Public Health and Sanitation.
(2009): Kenya Health Sector Satisfaction Survey Report.
40. Ministry of planning, national development and vision 2030. (2010): 2009
Population and Housing Census Results.
41. Mortazavi, S., Kazemi, M., Shirazi, A. and Aziz- Abadi, A. (2009): The
relationship between patient satisfaction and loyalty in the private hospital
industry. Iranian Journal of Public Health. 38(3): 60-69.
42. Muhondwa, E.P., Leshabari, M.T., Mwangu, M., Mbembati, N. and Ezekiel,
M.J. (2008): Patient satisfaction at the Muhimbili National Hospital in Dar es
Salaam, Tanzania. East Africa Journal of Public Health. 5(2): 67-73
43. Myburgh, N.G., Solanki, G.C., Smith, M.J. and Lalloo, R. (2005): Patient
satisfaction with healthcare providers in South Africa: the influences of race and
socio-economic status. International Journal for Quality Healthcare. 17(6): 473-
477.

84
44. Nathorst, B. J., Munck, I.M. and Eckerlund, I. (2001): An evaluation of the QSP
and QFP: two methods for measuring patient satisfaction. International Journal
for Quality Healthcare. 13:257-264.
45. Otani, K., Kurz, R.S. and Harris, L.E. (2005): Managing primary care using
patient satisfaction measures. Journal of Healthcare Management. 50:311-324.
46. Pascoe, G.C. (1983): patient satisfaction in primary care: a literature review and
analysis. Evaluation of program planning.6: 185-210.
47. Rahmqvist, M. (2001): Patient satisfaction in relation to age, health status and
other background factors: a model for comparison of care units. International
Journal for Quality Healthcare. 13(5): 385-390.
48. Rahmqvist, M. and Bara, A. (2010): Patient characteristic s and quality
dimensions related to patient satisfaction. International Journal for Quality
Healthcare. 2:86-92.
49. Rao, M., Clarke, A., Sanderson, C. and Hammersley, R. (2006): Patients’ own
assessments of quality of primary care compared with objective reco rds based
measures of technical quality of care: cross sectional study. British Medical
Journal. 333: 19-22.
50. Reker, D.M., Duncan, P.D., Horner, R.D., Hoenig, H., Samsa, J.P., Hamilton,
B.B. and Dudley, T.K. (2002): Post-acute Stroke Guideline Compliance Is
Associated With Greater Patient Satisfaction. Arch Phys Med Rehabil. 83: 750 –
756.
51. Sack, C., Schertag, A. and Lutkes, P. (2011): Is there an association between
hospital accreditation and patient satisfaction with hospital care? A survey of
37,000 patients treated by 73 hospitals. International Journal for Quality Health
Care. 3: 278-283

85
52. Schoenfelder, T., Klewer, J. and Kugler, J. (2011): Analysis of factors associated
with patient satisfaction in ophthalmology: the influence of demographic data,
visit characteristics and perceptions of received care. Journal of the College of
Optometrists. 31: 580-587.
53. Schoenfelder, T., Klewer, J. and Kugler, J. (2011): Determinants o f patient
satisfaction: a study among 39 hospitals in an in-patient setting in Germany.
International Journal for Quality in Health Care. 5:503 -509.
54. Sekandi, J.N., Makumbi, F.E., Kasangaki, A., Kizza, I.B., Tugumisirize, J.,
Nshimye, E., Mbabali, S. and Peters, D.H. (2011): Patient Satisfaction with
Services in Outpatient Clinics at Mulago hospital, Uganda. International Journal
for Quality Health Care. 5: 516-523.
55. Sitzia, J. and Wood, N. (1997): Patient satisfaction: a review of issues and
concepts. Social science and medicine. 45: 1829-1843.
56. Stewart M. (2001): Towards a global definition of patient centred care. British
Medical Journal. 322:444–45.
57. Tateke, T., Woldie, M. and Ololo, S. (2012): Determinants of patient satisfaction
with outpatient health services at public and private hospitals in Addis Ababa,
Ethiopia. African Journal of Primary Health Care and Family Medicine. 4(1):
article 383, 11 pages.
58. Tung, Y. and Chang, G. (2009): Patient satisfaction with and recommendation of
a primary care provider: Associations of perceived quality and patient education.
International Journal for Quality in Health Care. 21(3): 206-213
59. Van Koulil, S., Kraaimaat, F. W., Van Lankveld, W., Van Riel, P.L.C.M. and
Evers, A. W.M. (2009): A Patient’s Perspective on Multidisciplinary Treatment

86
Gain for Fibromyalgia: An Indicator for Pre-Post Treatment Effects? Arthritis
Care & Research. 61 (12) 1626–1632.
60. Wensing, M., Vingerhoets, E. and Grol, R. (2003): Feedback based on patient
evaluations: a tool for quality improvement? Patient Educ Couns. 51:149-53.
61. Wikipedia contributors. (2012): Wikipedia, The free Encyclopedia.
62. Whitehead M. (1990): The Concepts and Principles of Equity and Health.
Europe: World Health Organization, Regional Office.
63. Wong, E.L.Y., Leung, C.M., Cheung, W.L., Yam, C.H.K., Yeoh, E.K., and
Griffiths, S. (2011): A population-based survey using PPE-15: relationship of
care aspects to patient satisfaction in Hong Kong. International Journal for
Quality Health Care. 23(4): 390-396.
64. Woodside, A.G., N ielsen, R.L., Walters, F. and Muller, G.D. (1988): Preference
segmentation of health care services: the old- fashioned, value conscious, affluent
and professional want- it-all. Journal of Health Care Marketing. 8(2):14-24
65. Young, G. J., Meterko, M. and Desai, K.R. (2000): Patient satisfaction with
hospital care: effects of demographic and institutional characteristics. Medicare.
38: 325-34.
66. Zwier, A.G. and Clarke, D. (2001): Benchmarking patient satisfaction: do we
have a level playing field? New Zealand Health and Hospital Journal. January-
February: 21-24.

87
APPENDICES
APPENDIX 1: CLIENT CONSENT FORM
Introduction:
Good morning/afternoon. My name is Martin Mwangi Kimani, a student at Maseno
University’s School of Public Health and Community Development. I am doing a
survey amongst users of healthcare services at Busia District Hospital to evaluate the
services they offer. The aim of this study is to assess the determinants of patient
satisfaction with outpatient healthcare services at Busia district hospital.
Basis of participation:
You have been randomly selected to take part in this survey and all information that
you give will remain strictly confidential and will only be used for research purposes.
Your name will not appear anywhere in the study questionnaire. Your participation
will purely be voluntary. You will need approximately 20 minutes to respond to the
questions. Please note that you will not be exposed to any risks by participating in this
study and you have the right to withdraw from this study at any time if you are
uncomfortable.
Benefits:
Information from this study will be strictly for learning purposes. It may also be used
by The Ministry of Health, Busia district hospital and other stakeholders to improve
the quality of healthcare services provided. Your sincere and true response will
contribute to the achievement of the aim of this study.
88
Respondent’s consent:
The details pertaining to the said study have been adequately explained to me and I
am freely willing to be a participant.
Signature Date
Witnessed by Research assistant;
Signature Date
For any queries or further clarification, please contact:
Martin Mwangi Kimani
Postal Address: Maseno University, P.O BOX Private Bag, Maseno.
Mobile No: 0720242708
Email address: [email protected]
Thank you for your time and co-
operation. Yours Faithfully,
Martin Mwangi Kimani
89
APPENDIX 2: CLIENT EXIT INTERVIEW QUESTIONNAIRE
THE MASENO UNIVERSITY
PRIVATE BAG
MASENO- KEN YA
Date of interview
SOCIO-DEMOGRAPHICS
D1. Gender: Male Female
D2. Age of the respondent
18-25 years 46-55 years DON’T KNOW
26-35 years 56-65 years
36-45 years Over 65 years
D3. Highest level of education
No formal schooling Post-secondary school education
Primary education College education
Secondary school education University education
D4. Employment status
Permanent employment Self employed
Casual employment Unemployed
D5. Marital status
Married Single Divorced
90
D6. Place of residence
HEALTH RELATED
CHARACTERISTICS OF RESPONDENTS
Condition treated for:
Physically disabled:
Nature of visit:
MAIN QUESTIONNAIRE
SECTION ONE: Importance of service attributes (tick appropriately).
For this section, if 5 is “strongly agree”, 4 is “agree”, 3 is “neutral”, 2 is “disagree”
and 1 is “strongly disagree”, circle your appropriate response.
1.1 The following attributes regarding healthcare provision are important to me:
Attributes Tick appropriately
Friendliness of hospital staff 1 2 3 4 5
Knowledge and competence of staff 1 2 3 4 5
Treating you with respect 1 2 3 4 5
Guidance and information provided on your health needs 1 2 3 4 5
Cleanliness and tidiness of the health facility 1 2 3 4 5
Overall appearance of the staff 1 2 3 4 5
Cost of healthcare 1 2 3 4 5
Privacy and confidentiality 1 2 3 4 5
Accessibility and availability of healthcare 1 2 3 4 5
Waiting time before service 1 2 3 4 5
Return visitFirst visit
NOYES
91
Availability of medicines and other medical supplies 1 2 3 4 5
Time spent with the healthcare provider 1 2 3 4 5
SECTION TWO: General satisfaction with healthcare service.
For questions 2.1 to 2.4, if 5 is “strongly agree”, 4 is “agree”, 3 is “neutral”, 2 is
“disagree” and 1 is “strongly disagree”, tick your appropriate response.
2.1. All things considered, the service I have just received from the health care facility is excellent:
2.2. I am satisfied with the medical care I have received:
2.3. I have received the best healthcare as I expected from this health facility today:
1 2 3 4 5
2.4. I feel perfectly satisfied with the way I have been treated by the health providers at this health
facility today:
SECTION THREE: Immediate experience specific to places visited today. In this
section, if 5 is “strongly agree”, 4 is “agree”, 3 is “neutral”, 2 is “disagree” and 1 is
“strongly disagree”, please circle your appropriate response for the following
question.
1 2 3 4 5
1 2 3 4 5
1 2 3 4 5
92
3.1.I am perfectly satisfied with the service I have received at ( mention each
place visited separately) facility for their overall service?
Section visited today Tick appropriately
Enquiries/customer care 1 2 3 4 5
Card collection point 1 2 3 4 5
Accounts/cashier 1 2 3 4 5
General outpatient clinic 1 2 3 4 5
Laboratory 1 2 3 4 5
Pharmacy 1 2 3 4 5
x-ray 1 2 3 4 5
MCH/FP 1 2 3 4 5
VCT 1 2 3 4 5
Dental clinic 1 2 3 4 5
Physiotherapy 1 2 3 4 5
Orthopedic clinic 1 2 3 4 5
Occupation therapy 1 2 3 4 5
TB clinic 1 2 3 4 5
STI clinic 1 2 3 4 5
Specialists clinics 1 2 3 4 5
Others (specify) 1 2 3 4 5
93
SECTION FOUR: Technical quality and provider competence.
In this section, if 5 is “strongly agree”, 4 is “agree”, 3 is “neutral”, 2 is “disagree”
and 1 is “strongly disagree”, tick your appropriate response.
4.1. I think the hospital has the resources needed to provide complete medical care:
1 2 3 4 5
4.2.I think the hospital staffs are qualified to serve me adequately:
1 2 3 4 5
4.3.Doctors and nurses often do give me advice on ways to avoid illnesses and stay healthy:
4.4. Generally, I waited for reasonable time before being served:
4.5. Doctors and nurses spent sufficient time with me:
1 2 3 4 5
Medicines and other therapies prescribed (tick appropriately)
4.6. I received all the drugs prescribed to me by the clinician:
4.7.All the treatment/therapies recommended by the clinicians are available in this health
facility:
1 2 3 4 5
1 2 3 4 5
1 2 3 4 5
1 2 3 4 5
94
SECTION FIVE: Provider interpersonal aspects.
5.1. The doctors who treated me were interested in my well being:
5.2. The hospital staff are friendly:
5.3.The hospital staff treat me with respect:
5.4.The hospital staff adhered to privacy and confidentiality while treating me:
1 2 3 4 5
5.5 During my medical visits, I was always allowed to say everything I
thought was important:
5.6 Doctors were good in explaining the reason for medical tests:
5.7 Doctors were good in explaining the diagnosis to me:
5.8 Doctors used medical terms and explained what they meant:
5.9 Hospital staffs always listen to me:
5.10 I received explanation for any delay in getting a service:
1 2 3 4 5
1 2 3 4 5
1 2 3 4 5
1 2 3 4 5
1 2 3 4 5
1 2 3 4 5
1 2 3 4 5
1 2 3 4 5
1 2 3 4 5
95
5.11. I was involved in making decisions concerning my treatment: SECTION
SIX: Hospital milieu - physical environment,
accessibility, availability of service, convenience, cleanliness and
affordability.
6.1. This hospital is conveniently located:
6.2. I am able to get medical aid whenever I need it:
6.3. If I have a medical question, I can reach a doctor for help without any
problem:
6.4. I can easily access medical specialists in the hospital:
6.5. I had to pay more than i could afford for medical care:
6.6. Overall, the cost of healthcare services in this facility is reasonable:
6.7. This health facility’s buildings are well maintained:
6.8. Generally, this health facility is clean:
6.9. The facilities in this hospital are old fashioned:
1 2 3 4 5
1 2 3 4 5
1 2 3 4 5
1 2 3 4 5
1 2 3 4 5
1 2 3 4 5
1 2 3 4 5
1 2 3 4 5
1 2 3 4 5
1 2 3 4 5

96
SECTION SEVEN: Loyalty and recommendation of service.
7.1 This is the facility that I visit most often when I need healthcare:
7.2 Considering my experiences and opinions about this health facility, I would you recommend
the services it offers to other patients:
7.3 Considering my experiences and opinions about this health facility, I would continue to use
their services whenever need arises:
7.4 I would still choose this health facility over a private for profit health facility even
if my medical costs were taken care of:
1 2 3 4 5
THANK
YOU
FOR
YOUR
TIME AND
CO-OPERATION.
1 2 3 4 5
1 2 3 4 5
1 2 3 4 5

97
APPENDIX 3: UON/KNH ETHICS RESEARCH COMMITTEE’S
APPROVAL

98
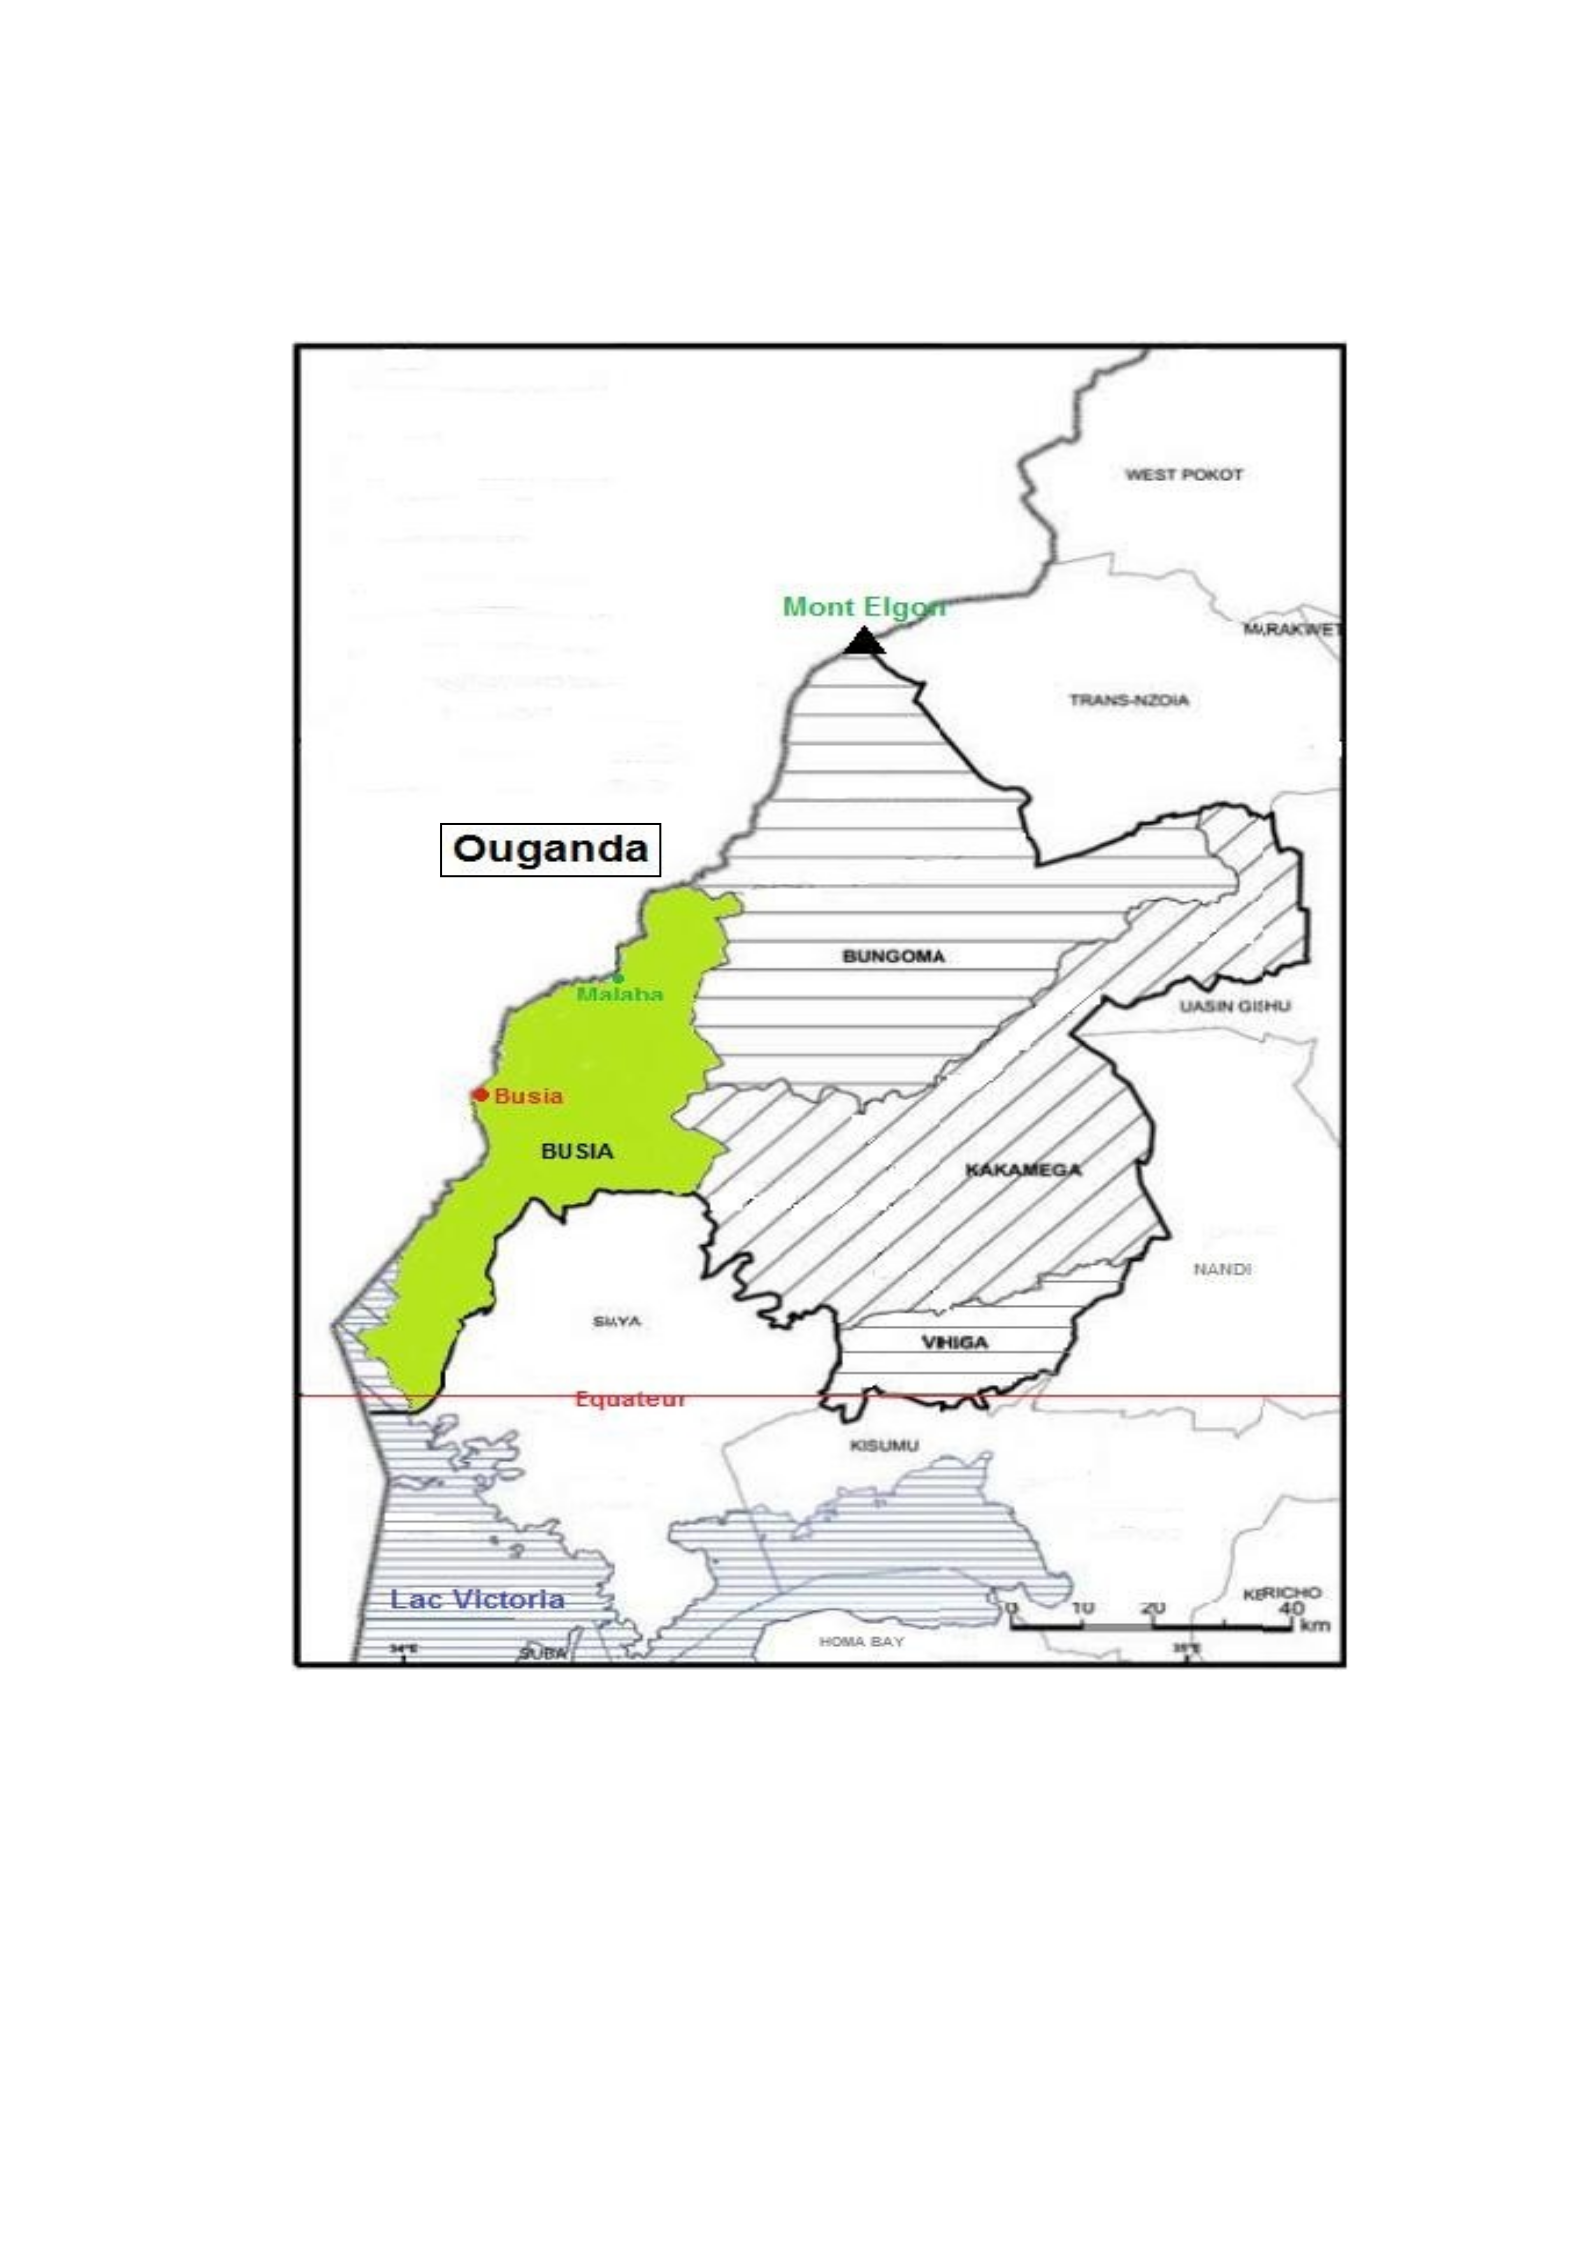
99
APPENDIX 4: MAP OF THE STUDY SITE – BUSIA DISTRICT HOSPITAL
UGANDA

