


Liberty University
Master of Public and Community Health
HLTH 507: Public Health Administration
Shean C. Cain
ID: L26083380
March 6, 2024
1

Abstract
The COVID-19 pandemic has significantly widened the inequity gap among
vulnerable populations. As a result, numerous articles have been written to highlight the
importance of an integrated approach between primary health care (PHC) and public health
(PH) to address these disparities. In the article “Addressing health inequity during the
COVID-19 pandemic through primary health care and public health collaboration: a
multiple case study analysis in eight high-income countries” it evaluates the collaboration
between PHC and PH across eight high-income countries.1 The article’s primary objective is
analyzing the different strategies to meet the health needs of vulnerable groups during the
pandemic. Results indicate varying degrees of success in implementing outreach strategies,
digital health assessments, and ensuring representation at the decision-making level. The
study concludes with recommendations for enhancing collaboration to improve health equity
and preparedness for future public health emergencies.
Keywords: COVID 19, primary health care (PHC), public health (PH), inequality
2

Policy Commentary
Critical Challenge
The focusing on how Primary Health Care (PHC) and Public Health (PH) can
collaborate to address the COVID-19-related health inequity gaps for vulnerable populations,
providing insights from eight high-income countries. However, the generalizability of this
research is hampered by a significant limitation, particularly about low- and middle-income
countries (LMICs).1 This focus on high-income settings presents a complex challenge given
that substantial structural, socioeconomic, and healthcare system disparities between these
and LMICs affect the direct application of the results. It is generally known that most high-
income nations have better healthcare infrastructure, more resourceful public health
programs, and efficient digital health systems than low-income nations.2 This improved
system of health cares allows them to execute sophisticated Primary Health Care (PHC) and
Public Health (PH) collaborations, extensive outreach strategies as well as digital healthcare
solutions that may not be feasible in LMICs owing to limited resources. Replicating strategies
successfully in affluent countries is difficult because of constrained healthcare financing,
inadequate medical personnel, and usually fragmented delivery systems within poor nations.
Moreover, socio-political context and cultural orientation in LMICs can significantly
influence the efficacy of health interventions. Differences may influence the success of PHC
and PH collaborations in governance structures, implementation frameworks for public health
policies, community involvement practices, and trust in healthcare systems.2 Mainstreaming
such providers into formal PHC or PH strategies would entail an in-depth understanding of
high-income-based approaches by adapting them accordingly. Finally, there is an enormous
digital divide between HHICS or rich countries versus LICs or poor ones due to one crucial
reason.3 This gap in technology represents a significant barrier when it comes to connecting
3

people with digital technologies, which are powerful tools during pandemics like COVID-19,
especially for contact tracing purposes among other activities done during outbreaks where
internet access might be an issue.
Extension of the stance
Vanden Bossche et al.'s work has described the necessity for functional integration
between PHC and PH to enhance equity within health care This message resonates well with
Christian teachings of loving one's neighbor, as evidenced in Matthew 25:35-40 where Christ
stresses to his followers that they must serve anyone marginalized or vulnerable to
marginalization as if they were doing it for Him alone. This viewpoint is further reaffirmed in
John 3:17-18, “If anyone has material possessions and sees a brother or sister in need but has
no pity on them, how can the love of God be in that person? Dear children, let us not love
with words or speech but with actions and in truth”.4 The biblical mandate supports PHC and
PH's functioning not as separate entities but as united efforts that seek to prioritize any group
in society, especially those most prone to risks.3 In support of this view, joint ventures and
societal health initiatives materialize into tangible scriptural principles at work. As such,
efforts try to tackle various factors affecting people's well-being and respond well with a
holistic approach proposed by the Bible teachings. For example, by pooling funds from both
sectors plus expertise and networks, there is enough financial base for comprehensive
programs meant not only for medical wants but also for economic status, social well-being,
and the welfare of an individual. According to Acts 4:32-35, “All the believers were one in
heart and mind. No one claimed that any of their possessions was their own, but they shared
everything they had”.4 Policies that provide food, shelter, and care for those suffering from
poverty, disease, or displacement are consistent with Jesus' injunctions about serving "the
4

least." Such projects are inherently driven by Biblical love and service—one of the finest
5

examples of healthcare collaboration becoming a significant expression of faith.
6
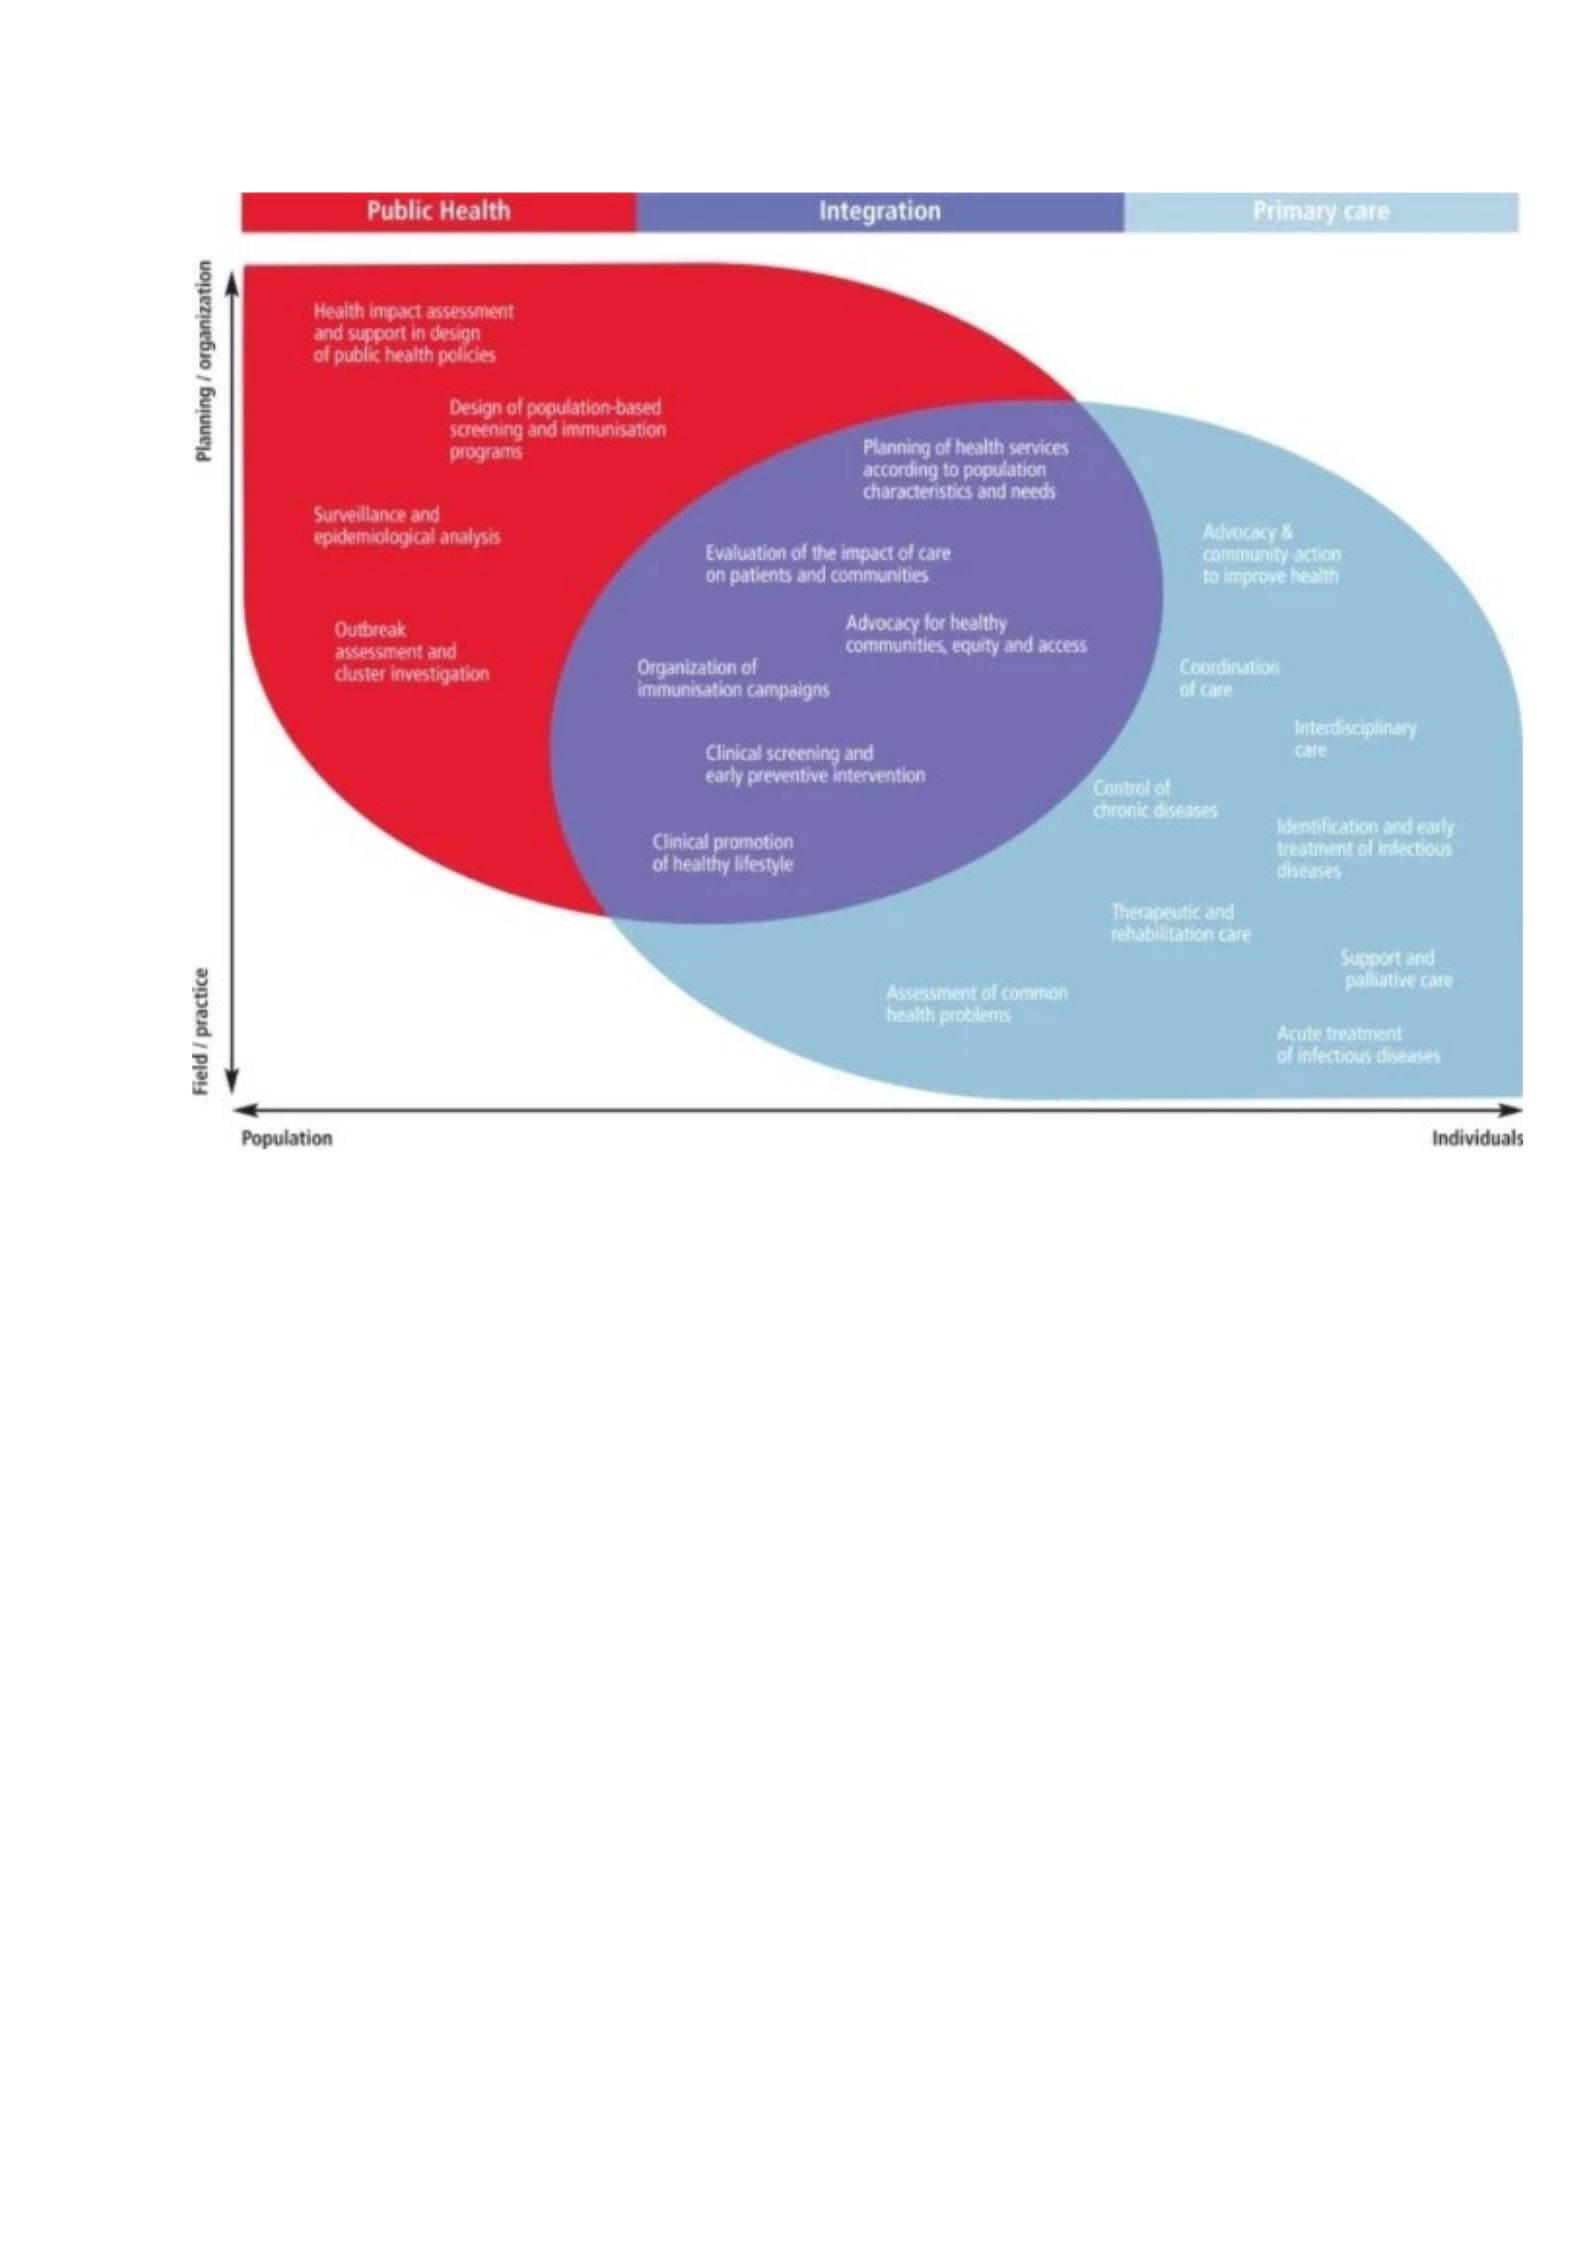
Figure 1.1 shows Interaction between public health and primary health care.1
Nehemiah's leadership qualities further highlight the importance of coming together
to solve health inequalities. In light of his people's welfare concerns, Nehemiah was proactive
in rebuilding Jerusalem's walls, emphasizing visionary leadership, community engagement,
and collective action to overcome them. Consequently, modern health policies could borrow
from Nehemiah's strategy of contemplative, prayerful moments among all segments involved
before mobilizing resources towards achieving collective goals and ensuring that all in the
society are involved. In this respect, policies requiring PHC and PH collaboration can seek
guidance from Nehemiah's example by creating a sense of mission unity by involving all
stakeholders actively and dealing with the barriers to equitable health in a determinedly
empathetic manner. This viewpoint is reemphasized in Ecclesiastes 4:9-10, which states “Two
7

are better than one, because they have a good return for their labor: If either of them falls
down, one can help the other up. But pity anyone who falls and has no one to help them up’.4
The bible clearly states the importance of coming together and giving a hand to those in
needy. This view is consistent with Nehemiah leadership style that emphasized togetherness
in restring Jerusalem. Moreover, Nehemiah's leadership highlights the importance of
stewardship and responsibility when managing resources for the common good.3 This means
using health resources judiciously within the context of integrated PHC/PH, ensuring that
interventions are fair, evidence-based, and meet community needs.2 This necessitates that
policies be designed transparently and accountable with a commitment to measurement and
reporting outcomes to promote health equity through such collaborations.
Application Of Experience
The connection between PHC and PH is a symbiotic relationship essential for
developing effective and fair health policies. This need becomes even more apparent when
you view it through the biblical perspective of this collective sinfulness and mercy/hope in
the case of Nehemiah. Nehemiah's steadfast care for his people and efforts to rebuild the
walls of Jerusalem are some of the most famous examples illustrating efficient community-
oriented leadership. Nehemiah 2: 10 states, “When Sanballat the Horonite and Tobiah the
Ammonite official heard about this, they were very much disturbed that someone had come to
promote the welfare of the Israelites”.4 The Bible highlights how important it is for a leader to
bear vision, be full of love, and make decisions for the public interest. Regarding health
policy, integration between PHC and PH is an expression of leadership akin to Nehemiah's
leadership in modern times. It means that healthcare systems should do more than merely
cure diseases because they must anticipate and manage risk factors in health, be alert to social
8
determinants, and ensure equal access to healthcare by everybody in society.3 This approach
is consistent with biblical precepts such as collective responsibility, where the well-being of
each person contributes to overall societal health.
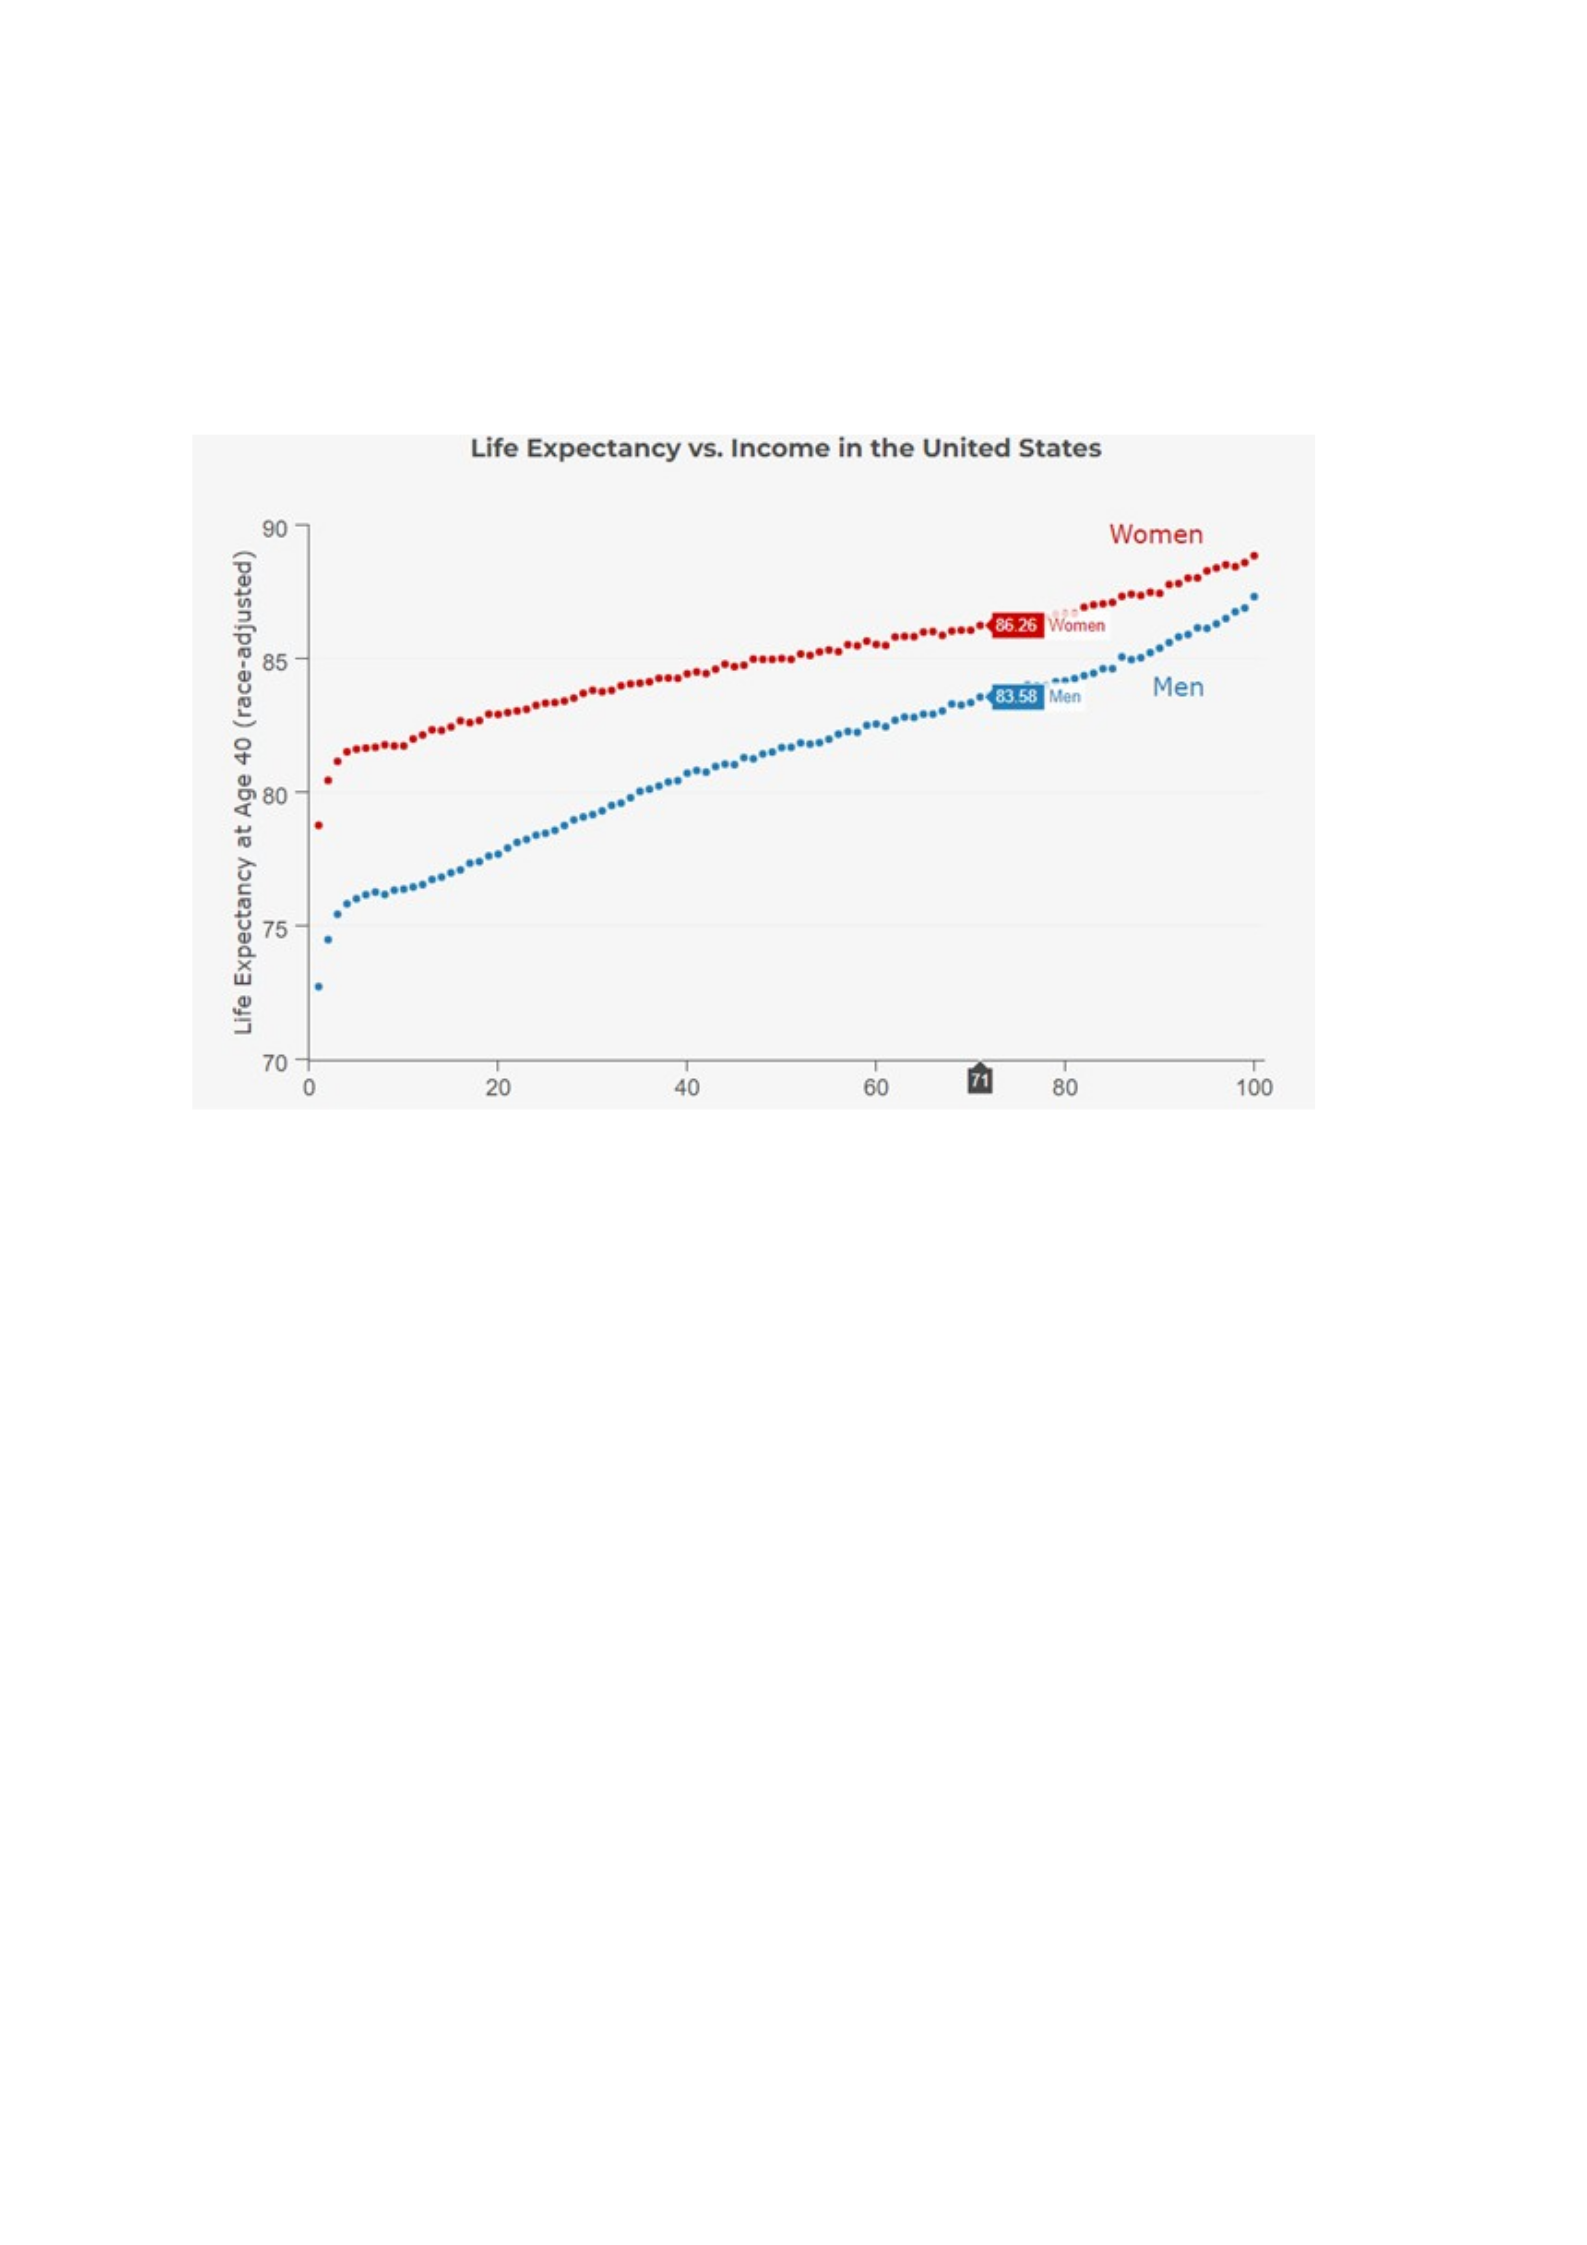
Figure 1.2 highlights health inequities based on income.7
Compassionate policies that reflect Christ's love for all must be developed equitably,
considering the diverse needs within communities while preserving human dignity
irrespective of individual worthiness. Galatians 6:2, “Carry each other’s burdens, and in this
way, you will fulfill the law of Christ.," illustrates the importance of a mutual support system
and shared responsibility toward our neighbors' welfare. Therefore, there can be effective
health policies that focus on ensuring that those who are marginalized or vulnerable receive
priority treatment without leaving anyone behind. Additionally, Mark 12:31 states that “You
shall love your neighbor as yourself.' There is no other commandment greater than these”.4
Loving one’s neighbor buttresses this call for empathic/just/equitable/equality-based policy
frameworks toward enhancing public health. These policies would seek better healthcare
outcomes and reduce poverty-related barriers such as lack of education or discrimination.
9

Meeting these requirements will enable policymakers to have health systems that are efficient
and effective but also deeply compassionate, thus reflecting the love of Christ for all human
beings.
Cultural Integration
Health interventions ought to be adaptable and considerate to the cultural peculiarities
in different communities, just as a body has different parts that have distinctive roles, but all
serve the common good. Respecting their unique identities and needs requires that planning
and implementation processes always consider communities. Romans 12:4-5 states, “For as
in one body we have many members, 1 and the members do not all have the same function, 5
so we, though many, are one body in Christ, and individually members one of another”.4 This
biblical teaching suggests that many members can form one body in Christ where each one
contributes differently depending on their gifts received; so, should global health adhere to a
principle like this calling for humility in approaching each community with willingness to
learn rather than imposing solutions on them. Furthermore, Luke 10:33-34, states, “But a
Samaritan, as he traveled, came where the man was; and when he saw him, he took pity on
him. He went to him and bandaged his wounds, pouring on oil and wine. Then he put the
man on his own donkey, brought him to an inn and took care of him”.4 This parable on the
Good Samaritan illustrates compassionate activities and concern for others who may be
different from oneself in culture or social class. It can serve as an analogy for the involvement
with communities, their specific health challenges, and how they should be addressed using
cultural competence5. Community involvement ensures that these policies not only take into
account our cultures but are also more likely to be accepted by others within our society.
In LMICs, cultural and social determinants significantly influence how health
interventions are designed and implemented. The vast cultural variations across these
10

countries make health strategies need to be tailor-made and sensitive to indigenous norms,
beliefs, values systems, etc.6 Through engaging communities, unique health
perceptions/patterns can be understood upon which culturally competent interventions can be
created. On top of that, equitable health policies must focus on some wider social
determinants such as education levels, income inequalities that exist in societies and access to
clean water sources or nutritious foods.
The study by Vanden Bossche et al. underscores the importance of teamwork between
PHC and PHC in dealing with issues of inequality in health, such as what was evident during
the COVID-19 pandemic. Extending these findings globally is essential for creating both just
and inclusive strategies that tend to reduce inequalities among various populations. In
developing a holistic approach, research, policy, and practice must consider all community’s
peculiarities and possibilities, leading to an effective, culturally sensitive intervention. The
future focus should be exploring whether these collaborative models can be applied in low-
and middle-income countries (LMICs), considering infrastructure limitations, funding
restrictions, or human resources constraints.
References
11

1. Vanden Bossche D, Zhao QJ, Ares-Blanco S, Peña MPA, Decat P, Kondo N, Willems
S. Addressing health inequity during the COVID-19 pandemic through primary health
care and public health collaboration: a multiple case study analysis in eight high-
income countries. International Journal for Equity in Health. 2023;22(1):171.
2. Garcia R. Social determinants of health. In: A Population Health Approach to Health
Disparities for Nurses: Care of Vulnerable Populations. 2022.
3. Hollinger DP. Race, Medicine, and Healthcare: A Christian Ethics Perspective.
Dignitas. 2023;30(2):4-9.
4. Holy Bible: New International Version. Zondervan; 2023.
5. Assefa Y, Gilks CF, Reid S, van de Pas R, Gete DG, Van Damme W. Analysis of the
COVID-19 pandemic: lessons towards a more effective response to public health
emergencies. Globalization and Health. 2022;18(1):10.
6. Brown RK, Kaiser A. Religious Ideology, Race, and Health Care Policy Attitudes.
Politics and Religion. 2021;14(4):764-786.
7. The Health Inequality Project. Health Inequality Project. Accessed March 4, 2024.
https://www.healthinequality.org/.
12

