


Empirical Analysis of the Case Studies
‘Now obviously the propositions of the system have reference to matters of empirical fact;
if they did not, they could have no claim to be called scientific’ (Parsons, 1949, p. 7)
The following six sections assess the sub-question ‘How are PA and sport spoken
about in strategies for the health-orientated promotion of PA?’ through the inquiry of the
whole analysis unit. The selected documents have first been explored through the use of key
words. In detail, the selected list of terms has been used to find the sections which assess the
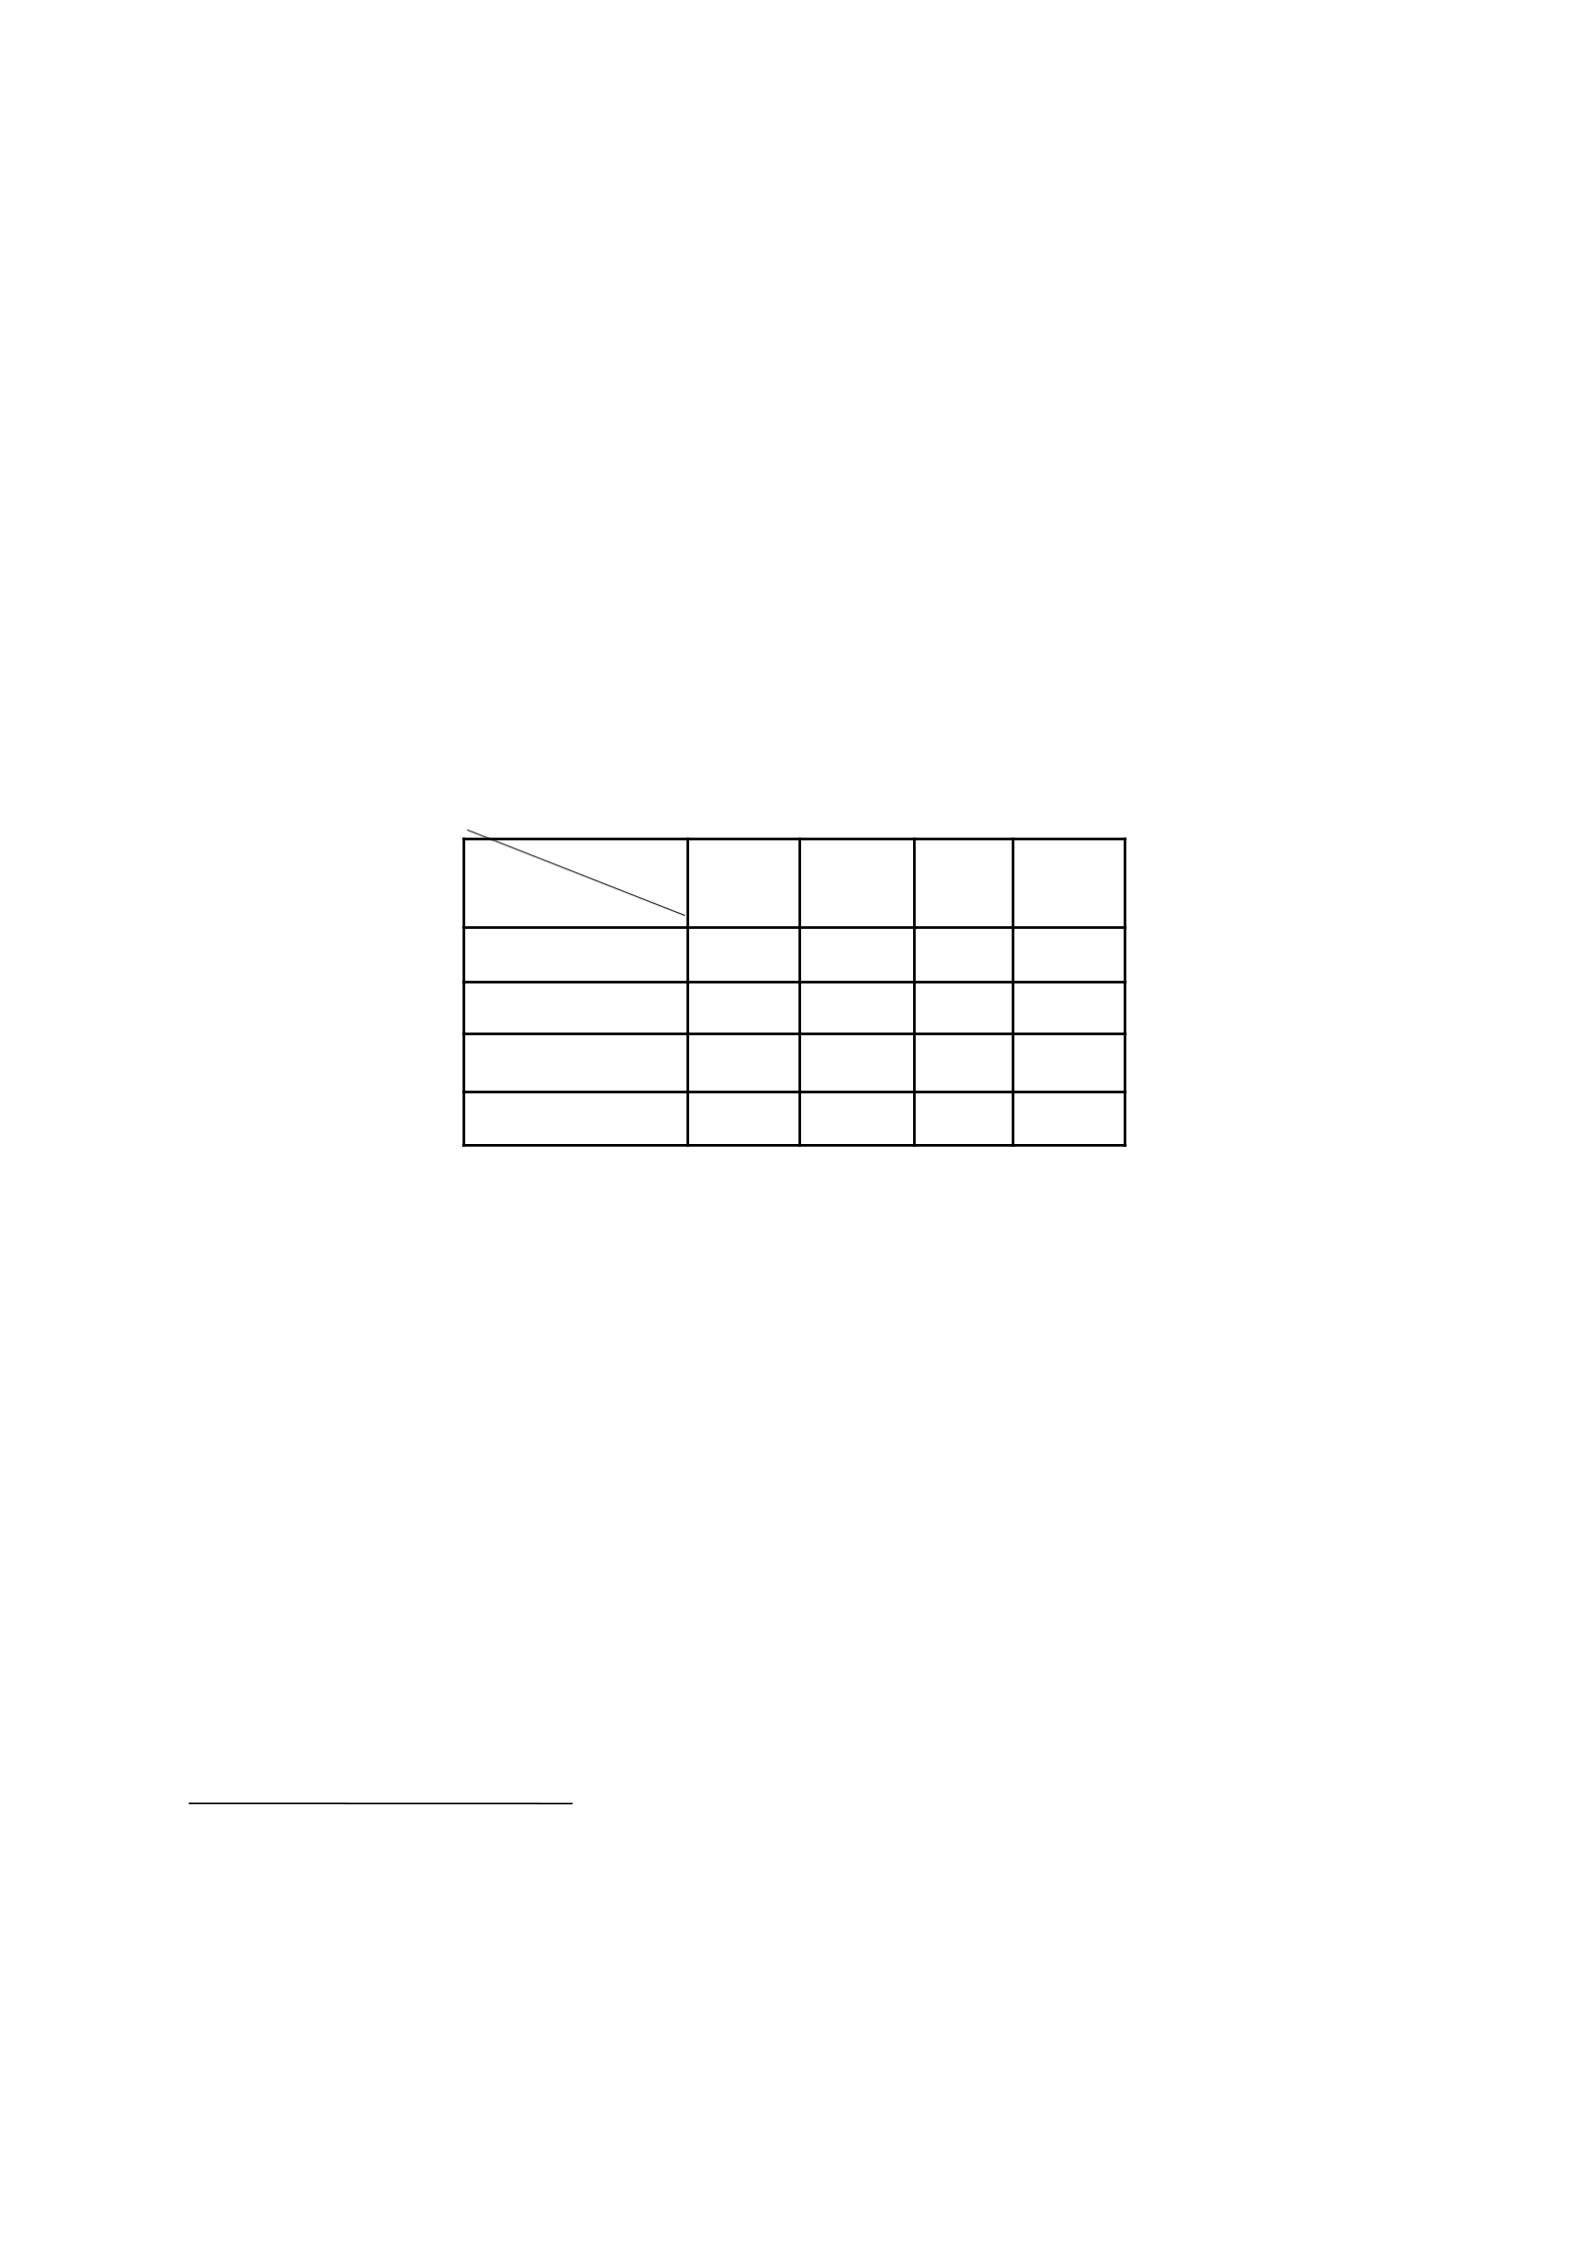
topics inquired within the documents. The distribution of the key words is summarised in the
table below:
Country
France
Germany
Italy Total
Key Word
Movement
35
498
28 561
Physical Activity
435 91 70 596
Sport
116
186
36 338
Total
586
775
134 1495
Figure 14 Key Words in the Case Studies
The contents of the sections identified have been investigated for assessing the
following queries198:
1. What is the recommended dose of PA?
2. What role do the sport organisations have?
3. Why is sport being delegitimised as a medium of health promotion?
4. How sound are the key concepts?
For each query a category (Lamnek, 1995, p. 192) has been developed for guiding the
process of content analysis. In this way, the chosen topics have been filtered from the texts
and a cross-section from the material has been created in order to allow for their evaluation
198 Even if the formulation of a research question is one of the first methodological steps when undertaking
research, its final form and especially the sub-questions and queries it raises have been revised and modified up
to the final steps of the research process. In fact, the operationalisation of a research question implies an
advanced status of the research, particularly if the sub-questions and queries are preliminary and/or connected to
each other or to the results of the empirical analysis. As a result of these facts, not every following query has
been established a priori but they have instead been developed as a result of the cyclic research process. In
particular: categories 1, 2 and 5 have been conceived a priori and in the light of the theoretical framework;
whereby categories 3 and 4 emerged as relevant a posteriori during the document analysis procedures.
124

(M
ayr
ing
,
20
03,
p.
89)
.
Thi
s
nat
ura
lly
de
vel
op
ed
in
a
sys
te
m
of
wi
der
sub
-
cat
eg
ori
es
est
abl
ish
ed
dur

ing
the
co
din
g
pro
ced
ure
s
for
the
me
ani
ngf
ul
org
ani
sati
on
of
the
inf
or
ma
tio
n
retr
iev
ed
in
the
do
cu
me
nts.
These category systems are each explained separately in the following four sections by
furnishing: insights on their logic and coding rules; anchor examples of the recording units;

reductions and classifications of the elements found within the documents; and, finally, a brief
comment on the results obtained. Because the four categories do not contain any insight into
the differences between the case studies, these are analytically compared in a separate section.
The comparison of the case studies has not been considered as a fifth category because its
proceeding is different: it does not analyse the documents but simply compares already
collected data. Because of their contents, these sections are characterised by a ‘dry’ register.
Its aim is to clearly and synthetically illustrate the procedures adopted and the results
obtained. Instead, the discursive and extensive interpretation of the data in the light of the
theoretical framework has been kept separate from this chapter and will be discussed in the
conclusions. This will extensively assess the main research question by generating
advancements in both the theoretical and empirical dimensions. The description and the
explanation of the social phenomenon will instead not constitute a theoretical model for the
normative optimal governance in PA promotion.
‘What is the Recommended Dose of PA?’
This section addresses the topic of the dose of PA recommended in the selected
health-strategies. This category has been created a priori, by reading primary and secondary
literature and in light of the theoretical framework. For a proper understanding of this section,
the operative distinction between sport and PA within this dissertation is fundamental: PA is a
broad concept defined as ‘any body movement produced by the skeletal muscles that results
in a substantial increase over the resting energy expenditure’ (Bouchard & Shephard, 1994, p.
77); Sport199 is a mode of physical activity branded by being recreational, governed by rules
and orientated towards performance (modified version of Heinemann, 2007, p. 56). This
characterisation points out some practical characteristics of sport activities which differentiate
them from PA: they normally require planned (leisure) time, special fields, equipment and/or
partners and their intensity is unpredictable, often fluctuate and tend to be high.
This section categorises and analyses pieces of text that give advices on the
characteristics of the dose of PA. Only the segments which respect the following
requirements have been considered as a recording unit:
−Clarity: the segments need to be explicit and clearly expressed without either possible
misunderstandings or the need for interpreting the concepts;
−Comprehensiveness: the segments need to assess at least three of the five200 characteristics of
PA. This choice has been taken a posteriori after the explorative step. The reason is that
recommendations containing two characteristics of PA were far too vague to constitute a base
for the analysis of the recommended doses of PA, but recommendations containing four or
five characteristics of PA were too few to embody the documents trend.
The first example provides information about the typology (a brisk walk), the duration
(30 minutes) and the frequency (5-6 times a week) of PA. Even if it does not furnish
information on the intensity (the adjective brisk has not been considered a sufficient clue) and
continuity, it respects the guidelines explained above and has been accepted as a valid
recording unit. Instead, the second example only provides information on frequency (daily)
and continuity (regularly), but no clues about typology, intensity or duration. For this reason it
is not considered to have satisfied the guideline of this category and has therefore been
discarded.
Distribution of the Recording Units
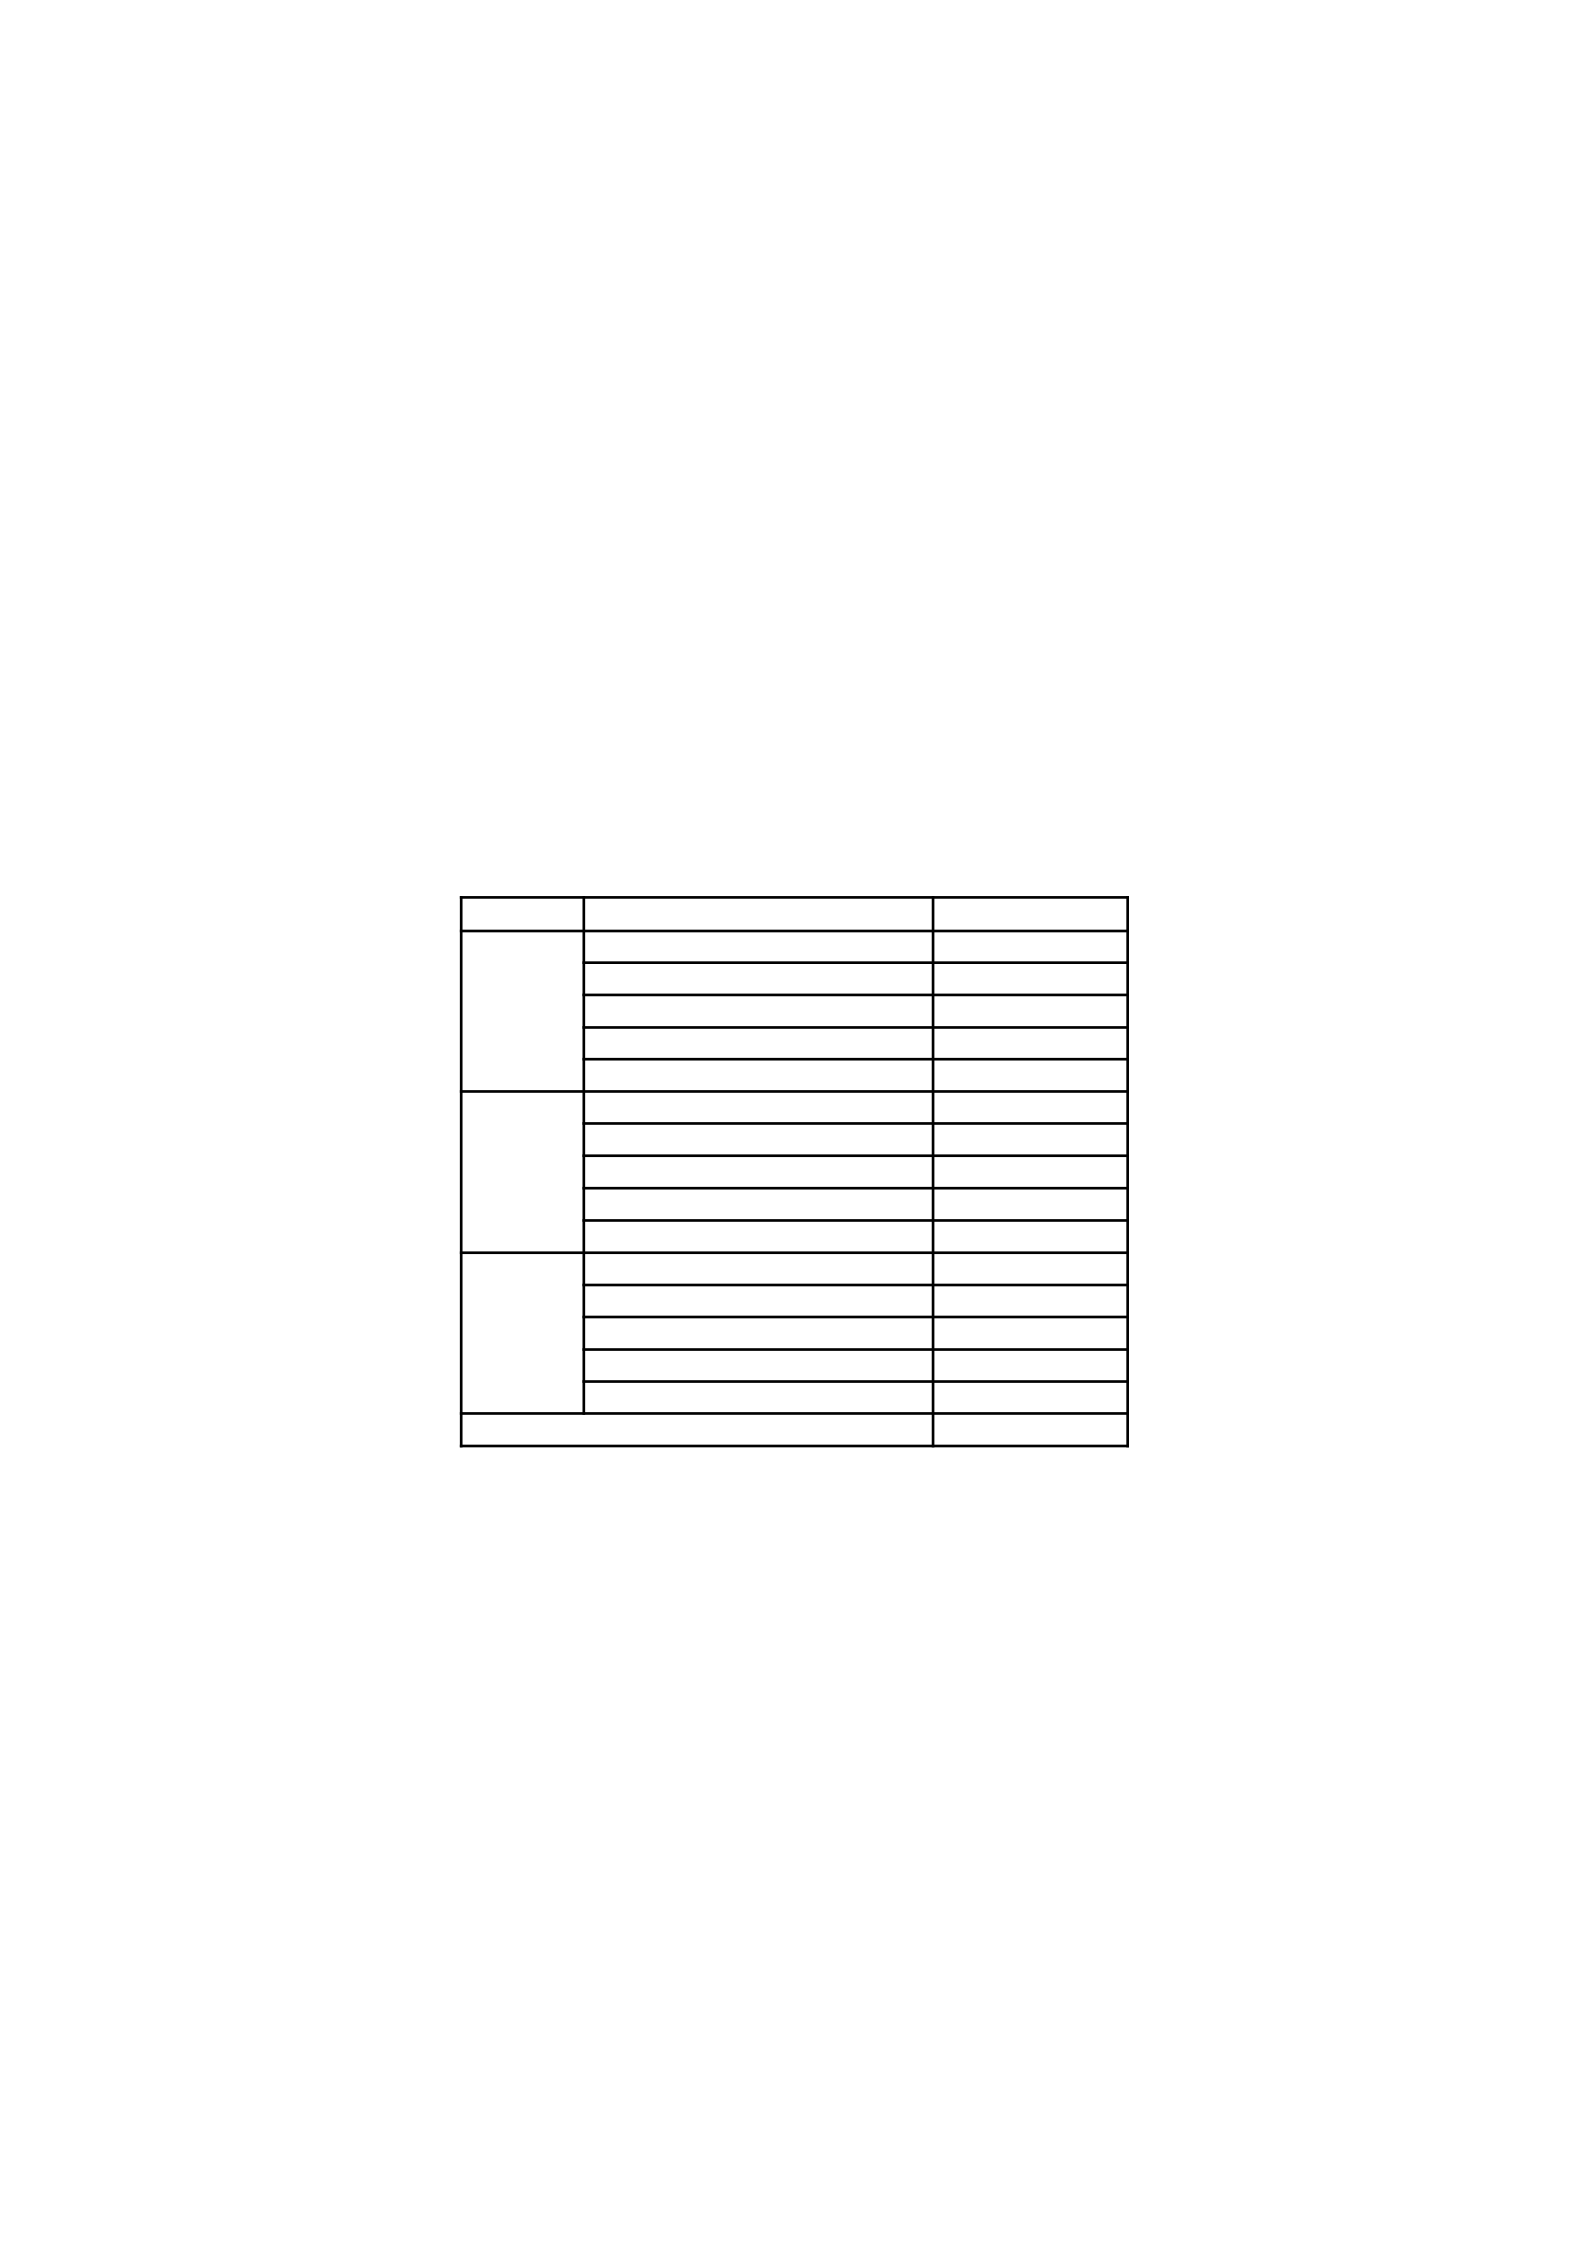
By following the guidelines above, 53 recommendations on the dose of PA have been
found. These recording units are distributed as in the following table:
Nation
Document Recording unit
PNNS1 2001-2005 1
PNNS2 2006-2010 3
France PNNS3 2011-2015 2
Health comes by moving 12
Physical Activity and Health
16
Mentally Fit in Old Age 3
INFORM
0
Germany
Active for Myself
3
Advisor on Health Care
5
National Health Objective 1
PSN 2006-2008 0
PSN 2011-2013 0
Italy
Pages of Health
3
Make Gains in Health 2
Gaining Health in 4 moves
2
Total
53
Figure 15 Distribution of Recommendations on the Dose of PA
It can be observed that three documents do not contain any recommendations at all on
the dose of PA, even if one of their aims (or, in the case of the strategy ‘IN FORM’, its
principal aim) is the promotion of PA. Almost all the rest of the documents (9) contain one to
127

three suggestions on the dose of PA. In three cases more recommendations are contained (5,
12 and 16).
Results per Population Segment
For the purpose of this dissertation, it is useful to separate the advice on the dose of
PA upon the base of the age segments of the population targeted by the recommendation. In
fact, during the analysis, numerous recommendations were detected that are directed to
particular age groups. The creation of separate categories has been considered necessary for
correctly summarising the meanings of the documents. A summary of the characteristics of
the PA suggested for each of these segments will now be separately commented upon:
−Children and youth: within the documents, four recommendations for children and
teenagers have been found. The duration of the suggested PA is of 60 minutes or more
(just one recommendation refers to a smaller amount of time) with a moderate or high
intensity and a frequency between three and seven times a week. The typology of the
activities entails a mix of sport-orientated activities (2) and PA in general (2). Collective
team sports are advised once, but just for 20 minutes three or more times a week. There
are no accounts on continuity.
−Adults: the ten recommendations for adults are characterised by an averagely lower
intensity and a shorter length than the one for children and teenagers. Regarding the
frequency, the most fragments advise PA seven times a week. The typology of activities
varies from PA in general (2) to exercise and sport (7). In five cases the recommendations
refer to endurance sport activities like running, swimming or cycling. However, team
sports are never mentioned and there is no reference to traditional-competitive sport
activities. A regular continuity is mentioned three times.
−The elderly: the frequency, duration and intensity recommended to the elderly are reduced
when compared to the previous two groups. The activities contained in the seven
recommendations are in four cases sport-orientated activities and in three cases everyday
activities. Also in this category there are no indications of continuity.
Results per Characteristic of PA
An analysis of the date obtained on every single characteristic of the dose of PA has
been considered useful in obtaining a focused overview of them. The following observations
can be made:
−For the mode of PA, many recommendations (15) don’t specify the mode of PA to be
carried out at all. Walking is recommended most frequently (11 times) and, in general, the
examples of mode furnished often regard everyday activities (20) like climbing stairs or
cycling to the workplace. Sport is recommended alone (3) or together with a broader set of

physical activities (12). However, collective sport games are mentioned only twice: in the
other cases endurance sport activities like swimming, cycling or jogging are referred to. In
summary, the majority of the recommendations refer to PA in general or everyday PA but
sometimes leisure activities are specifically referred to or of a mix of both.
−Continuity is, even if the international guidelines underline the importance of a ‘life-
course’ approach (WHO, 2004, p. 4) very rarely spoken about. In fact, a vague reference
to this topic has been found three times in the 53 recording units about the dose of PA.
−For the purposes of frequency, the recording units almost always offer a reference to the
frequency of the activities (46). Most recommended (33 times) is the practicing of PA on a
daily basis. A lower frequency is advised 14 times and in most of these cases, a leisure
activity is recommended (8) or the recommendations are directed towards the elderly (6).
In summary, the majority of the recommendations recommend PA being practised every
day and other suggestions refer to special cases.
−Regarding duration, the recording units almost always offer a reference to the length of
the activities (46). The most common recommendation is to do PA for at least for 30
minutes (17 times) or for 30 minutes (15 times). Exceptions to this tendency are seven
recommendations of a higher length and nine recommendations of a shorter duration.
−The intensity is assessed 29 times in the coded segments. The most recommendations refer
to moderate intensity (17). A higher intensity is recommended sometimes (5) for children
and teenagers (2) or for a shorter length than the normally advised 30 min (3). A
201 ‘At least 30 minutes of regular, moderate-intensity physical activity on most days’ (WHO, 2004, p. 4).

lower intensity is sometimes (4) recommended to the elderly (1) or for a longer duration than
the normally advised 30 min (3).
Reflection of the Results
In addition to explanations regarding the health effects of PA or the dangers connected to
PI, indications of the dose of PA are extremely relevant within the discussion on PA promotion
because they assess what people concretely should do to keep themselves fit through PA.
Furthermore, the scientific literature and the documents analysed often state that simple and
concrete recommendations regarding the form and quantity of PA to be carried out should be
provided through strategies for the promotion of PA (Bauman & Craig, 2005, p. 3; German
Ministry of Health & German Ministry of Nutrition, 2008, p. 21; WHO, 2004, p. 8).
However, the treatment of this topic within the analysed documents is not obvious. In
fact, the modern discussion of the dose of PA entails different and contradictory phenomena.
Because of the health system’s natural orientation and the consolidation of the idea that daily
moderately intense physical activity is sufficient for health benefits (Oja, 2004, p. 169), the role
of sport activities is becoming increasingly ambiguous in the rhetoric of the promotion of PA
(Michelini & Thiel, 2014 - Forthcoming). On the other hand, sport has been and is still the
backbone of the discussion of PA promotion. Last but not least, the double ambiguity concerning
the key terms of ‘PA’, ‘health’ and their interaction detected in the discourse concerning the
effects of PA on health makes an in depth analysis of the characteristics of PA discussed in the
documents mandatory. In fact, the analysis of the recommended dose of PA overwhelms the
vagueness of the indications, which only generally characterise the amount and typology of
PA.202
In summary, most of the documents (12/15) analysed contain recommendations
regarding the dose of PA to be carried out. By observing the advice and comparing it between
the segments of population, one can see that the recommended dose of PA has a longer duration
and a higher intensity for children and teenagers and decreases for adults or for everyone and is
even further reduced for the elderly. However, the recording units analysed demonstrate
imprecision and ambiguity with regards to certain topics and an almost total lack of indication
about continuity. Furthermore, the recommendations are often not connected with each other so

that it is difficult to understand whether the activities should substitute each other, or whether
they could be mixed and if so, how.
Often the recommendations embody the WHO’s standard ‘30 minutes of moderate
activity every day’ (WHO, 2004, p. 4). As previously affirmed, this format does not offer a clear
point of connection for the cooperation of the sport system because it is not compatible with
intensity, duration and frequency of most sport activities, for example those carried out in sport
clubs. Nevertheless, ‘sport’ and sport activities are often mentioned alone or with other activities
as mode of PA (18) within the recommendations. However, by reviewing the 13
recommendations, which contain concrete examples of the typology of sport to be practiced,
team sport is only recommended twice together with other activities. Instead, the other cases (11
times) all refer to endurance activities like cycling, swimming or jogging. Furthermore, the
recommended duration for collective sport disciplines is very short: only 20 minutes. Again, this
is extraneous to the format traditionally offered by sport organisations for these disciplines. This
contradiction can be explained by assuming that sport is still - as an abstract term - semantically
connected with health; on the other hand it is - in its traditional-competitive form - increasingly
marginalised as a medium of health (Michelini & Thiel, 2012). The documents analysed are a
vivid example of this trend: even if the term ‘sport’ is constantly mentioned, the analysis shows
that the practices recommended are never commensurable with classical sport format or
practicable in sport organisations. For this reason, a further analysis focused on the role of sport
organisations in health-orientated strategies for the promotion of PA has been considered
necessary.
References
British Medical Association. (1992). Cycling: Towards health and safety. Oxford: Oxford
University Press.
Brown, D. W., Balluz, L. S., Heath, G. W., Moriarty, D. G., Ford, E. S., Giles, W. H. et al.
(2003). Associations between recommended levels of physical activity and health-related
quality of life. Findings from the 2001 Behavioral Risk Factor Surveillance System
(BRFSS) survey. Prev Med, 37(5), 520-528.
Brown, D. W., Brown, D. R., Heath, G. W., Balluz, L., Giles, W. H., Ford, E. S. et al. (2004).
Associations between physical activity dose and health-related quality of life.
Medicine and science in sports and exercise, 36(5), 890.

Bunton, R. (1997). Popular health, advanced liberalism and good housekeeping magazine. In A.
Petersen & R. Bunton (Eds.), Foucault, health and medicine (223-248). London:
Routledge.
Busch, A. J., Barber, K. A., Overend, T. J., Peloso, P. M. & Schachter, C. L. (2007). Exercise for
treating fibromyalgia syndrome. Cochrane Database of Systematic Reviews(4),
CD003786. doi: 10.1002/14651858.CD003786.pub2
Cachay, K. (1988). Sport und Gesellschaft: Zur Ausdifferenzierung einer Funktion und ihrer
Folgen [Sport and Society: On the differentiation of a function and its consequences].
Schorndorf: Hofmann.
Cachay, K. (1990). Versportlichung der Gesellschaft und Entsportung des Sports -
Systemtheoretische Anmerkungen zu einem gesellschaftlichen Phänomen [The
sportification of society and the de-sportification of sport - System theoretical reflections
on a social phenomenon]. In H. Gabler & U. Göhner (Eds.), Für einen besseren Sport
[For a better sport] (97-113). Schorndorf: Hofmann.
Cachay, K. & Kastrup, V. (2006). Professionalisierung und De-Professionalisierung der
Sportlehrerrolle [Professionalisation and de-professionalisation of physical education
teacher's role]. Sport und Gesellschaft, 3(2).
Cachay, K. & Thiel, A. (1999a). Ausbildung ins Ungewisse? Beschäftigungschancen für
Sportwissenschaftlerinnen und Sportwissenschaftler im Gesundheitssystem [Uncertain
education? Employment opportunities for sport scientists in the health system]. Aachen:
Meyer&Meyer.
Cachay, K. & Thiel, A. (1999b). Vom Medizin- zum Gesundheitssystem -
Professionalisierungschance für Sportwissenschaftlerinnen und Sportwissenschaftler
[From the medicinal to the health care system - Professionalisation opportunities for
sport scientists]. Sportwissenschaft, 29(2), 143-157.
Cachay, K. & Thiel, A. (2000). Soziologie des Sports: Zur Ausdifferenzierung und
Entwicklungsdynamik des Sports der modernen Gesellschaft [Sociology of sport: On the
differentiation and dynamics of the development of sport in modern society]. Weinheim:
Juventa-Verlag.
Cachay, K., Thiel, A. & Kastrup, V. (2010). Professionalisierung des Sportlehrerberufs
[Professionalisation of sport-related employments]. In N. Fessler, A. Hummel & G.
Stibbe (Eds.), Handbuch Schulsport (245-255). Schorndorf: Hofmann.
Cannon, G. (2004). Why the Bush administration and the global sugar industry are determined to
demolish the 2004 WHO Strategy on diet, physical activity and health. Public health
nutrition, 7(3), 369 - 380.
Caspersen, C. J., Christenson, G. M. & Pollard, R. A. (1986). Status of the 1990 physical fitness
and exercise objectives - Evidence from NHIS 1985. Public health reports, 101(6), 587-
592.
Caspersen, C. J., Powell, K. E. & Christenson, G. M. (1985). Physical activity, exercise, and
physical fitness: Definitions and distinctions for health-related research. Public health
reports, 100(2), 126-131.
Castles, F. (Ed.). (1993). Families of nations: Patterns of public policy in western
democracies. London: Dartmouth Publishing Company Ltd.
Castles, F. & Mitchell, D. (1993). Worlds of welfare and families of nations. In F. Castles (Ed.),
Families of nations: Patterns of public policy in Western democracies (93-128). London:
Dartmouth Publishing Company Ltd.
Caudwell, J. (Ed.). (2006). Sport, sexualities and queer/theory. London: Routledge.

Cavill, N., Kahlmeier, S. & Racioppi, F. (2006). Physical activity and health in Europe:
evidence for action: World Health Organization.
CDC. (1993). Prevalence of Sedentary Lifestyle - Behavioral Risk Factor Surveillance System,
United States, 1991. Morbidity and Mortality Weekly Report, 29, 576-579.
http://www.cdc.gov/mmwr/preview/mmwrhtml/00021313.htm
CDC. (2000). Measuring Healthy Days: Population Assessment of Health-related Quality of
Life. Atlanta, Georgia: CDC.
CDC & ACSM. (1995). Physical activity and public health. A recommendation from the Centers
for Disease Control and Prevention and the American College of Sports Medicine.
Journal of the American Medical Association, 273, 402-407.
Collin, F. (2008). Konstruktivismus für Einsteiger [Constructivism for beginners] (1st ed.).
Stuttgart: UTB GmbH.
Conn, V. S., Hafdahl, A. R., Porock, D. C., McDaniel, R. & Nielsen, P. J. (2006). A meta-
analysis of exercise interventions among people treated for cancer. Support Care Cancer,
14(7), 699-712. doi: 10.1007/s00520-005-0905-5
Conrad, P. (1992). Medicalization and social control. Annual Review of Sociology, 18, 209-232.
Conrad, P. & Schneider, J. W. (1980). Deviance and medicalization: From badness to
sickness. Philadelphia: Temple University Press.
Corbetta, P. (1999). Metodologia e tecniche della ricerca sociale [Methodology and techniques
of social research]. Bologna: il Mulino.
Craft, L. L., Vaniterson, E. H., Helenowski, I. B., Rademaker, A. W. & Courneya, K. S. (2012).
Exercise effects on depressive symptoms in cancer survivors: a systematic review and
meta-analysis. Cancer epidemiology, biomarkers & prevention, 21(1), 3-19. doi:
10.1158/1055-9965.epi-11-0634
Crawford, R. (1980). Healthism and the medicalization of everyday life. International Journal of
Health Services, 10(3), 365-388.
Daley, A., Jolly, K. & MacArthur, C. (2009). The effectiveness of exercise in the management of
post-natal depression: systematic review and meta-analysis. Fam Pract, 26(2), 154-162.
doi: 10.1093/fampra/cmn101
Danzon, M. (2004). WHO - Diet and physical activity : the public health debate. European
Journal of Public Health, 14(3), 336.
Dauer, V. P. & Pangrazi, R. P. (1975). Dynamic Physical Education for Elementary School
Children. Minneapolis: Burgess Publishing Company.
Daugbjerg, S. B., Kahlmeier, S., Francesca, R., Martin-Diener, E., Martin, B., Oja, P. et al.
(2009). Promotion of physical activity in the European region: content analysis of 27
national policy documents. Journal of Physical Activity and Health, 6(6), 805-817.
Dawber, T. R., Meadors, G. F. & Moore Jr, F. E. (1951). Epidemiological approaches to heart
disease: The Framingham Study. American Journal of Public Health, 41(3), 279-286.
De Wachter, F. (1983). Spielregeln und ethische Problematik [Rules of the game and ethical
problems]. In H. Lenk (Ed.), Aktuelle Probleme der Sportphilosophie (278-294).
Schorndorf: Hofmann.
Defrance, J. & Renard, D. (2003). Sport and the welfare state in France. In K. Heinemann (Ed.),
Sport and welfare policies : 6 European case studies (219-252). Schorndorf: Hofmann.
Demetriou, Y. (2012). Health promotion in physical education. (PhD), Eberhard-Karls-

Universität Tübingen, Tübingen. Retrieved from
http://nbn-resolving.de/urn:nbn:de:bsz:21-opus-64271
Department for Culture, Media and Sport & Strategy Unit. (2002). Game plan: A strategy for
delivering government’s sport and physical activity objectives. DCMS/Strategy Unit,
London.
Diehl, K., Thiel, A., Zipfel, S., Mayer, J., Litaker, D. G. & Schneider, S. (2012). How healthy is
the behavior of young athletes? A systematic literature review and meta-analyses.
Journal of Sports Science and Medicine, 11, 201-220.
Diehl, K., Thiel, A., Zipfel, S., Mayer, J. & Schneider, S. (2012). Substance use among elite
adolescent athletes: Findings from the GOAL Study. Scandinavian Journal of Medicine
& Science in Sports, n/a-n/a. doi: 10.1111/j.1600-0838.2012.01472.x
Diener, E., Suh, E. M., Lucas, R. E. & Smith, H. L. (1999). Subjective well-being: Three
decades of progress. Psychological bulletin, 125(2), 276.
Digel, H. (1990). Die Versportlichung unserer Kultur und deren Folgen für den Sport - Ein
Beitrag zur Uneigentlichkeit des Sports [The sportification of our culture and its impact
on sport - An essay on the inauthenticity of sport]. In H. Gabler & U. Göhner (Eds.), Für
einen besseren Sport [For a better sport] (73-96). Schorndorf: Hofmann.
Digel, H. (1995). Was ist der Gegenstand der Sportwissenschaft? [What is the subject of sport
science?]. In H. Digel (Ed.), Sportwissenschaft heute. Eine Gegenstandsbestimmung (1-
18). Darmstadt: Wissenschaftlichen Buchgesellschaft.
Digel, H. & Barra, M. (2004). Hochleistungssport in Italien [Professional sport in Italy].
Weilheim/Teck: Bräuer.

