


1
Chapter 1: Introduction to the Study
Introduction
Domestic violence is a detrimental, widespread phenomenon that impairs family
bonding relationships with children. This impairment can often result in emotional pain
that inevitably leads to physical abuse and poor developmental processes (Foshie et al.,
2016; Margolin & Gordis, 2000). Domestic violence affects a large portion of the
adolescent population in America, yet it is problematically difficult to determine the
exact extent of its devastating effects. Exemplifying this issue, the U.S. Department of
Justice Bureau of Justice Statistics (DJBJS; 2000) proposed that domestic violence can be
perpetrated among current or former spouses, parents, or nonmarital partners in the home
where children live, but failed to mention how domestic violence influences the behavior
of adolescents who have witnessed the overwhelming violent events. On the other hand,
the U.S. Department of Justice (2000; Jan, Adeline, Angela, Danielle, & Deborah, 2015)
and the National Crime Victimization Survey (1999) reported that domestic violence
affects not only the direct victims but also witnesses to the event.
Because of these issues with measuring the influences of domestic violence,
estimates of the instances of domestic violence are difficult to determine. Specifically, the
precise incidence of domestic violence in American adolescents’ responses is nebulous
(Compton, 2010). There are several reasons for the lack of clarity in the data: (a) not all
incidences of domestic violence affecting adolescents are reported; (b) even on surveys
that purport to investigate this national epidemic crisis, there are no social scientists
whose sole duty is to gather information on this topic; and (c) scholars disagree on the

2
definition of domestic violence and its effects on adolescents’ resilience (Foshee et al.,
2016).
Nevertheless, research indicates that the impact of domestic violence on
adolescents’ emotional response is one of the prevalent social diseases in America.
Despite issues which may exclude many victims of domestic violence from being
acknowledged, Compton (2010), Giles (1998), and Carlson (2003) revealed an estimated
900,000 victims of violence with at least 160,000 fatal bodily injuries and hospitalization
among women and adolescents. Moreover, the results of this study indicated that
domestic violence is not limited to one socio-cultural or socio-economic background,
although it may vary along several lines, including race, gender, and age (see Bureau of
Justice Statistics, 2000; Jan et al., 2015). FBI homicide data also confirmed that domestic
violence has a significant effect on adolescents (Compton, 2010). Moreover, the effects
and outcomes of exposure to domestic violence can translate to individuals’ experiences
as young adults (Widom & Wilson, 2015). Therefore, it is clear that domestic violence is
an issue of epidemic proportions that may affect young adults’ resilience. These effects
are evidenced firsthand in many foster homes and treatment facilities (Carney, Buttell, &
Dutton, 2007; Compton, 2010).
Background
After many years of research on domestic violence, it appears that this social
travesty is increasing within American society (Beverly et al., 2015; Creswell, 2008).
Furthermore, poor definitions, poor research surveys, and poor methodologies in research
about domestic violence have opened doors for criticism (Brookmeyer, Fanti, & Henrich,

3
2006; Karol, Jeffrey, & Cory, 2015). Frustratingly, current data cannot even accurately
estimate domestic violence victims. For these reasons, Allen and Allen (2006) and Joyce,
Barros, Cafferky, and Johannes (2015) suggested that an estimated 3.3 million children
will be exposed to parental violence. English, Edleson, and Herrick (2007) and Vasquez-
Salgado, Greenfield, and Burgos-Cienfuegos (2015) suggested that most research
provides generalized findings based on old data and outdated views of domestic violence
rather than identifying specific issues affecting present day American families. Because
of the neglect in this area, child maltreatment, child abuse, neglect, sexual abuse, physical
abuse, and other forms of violence between family members continue to proliferate
(Allen & Allen, 2006; Monique, 2015). Moreover, this violence can be passed on
between generations (Widom & Wilson, 2015).
Thus, there existed a significant challenge to the accuracy of data that predicted
young adults’ resilience. The proliferation of domestic violence and the culture which
allows it to perpetuate have not only affected law makers’ and practitioners’ views, but
have also misled the public opinion about domestic violence and its victims (Karol et al.,
2015). Further study was necessary to eliminate this continuing problem (Karol et al.,
2015). Specifically, there was a gap in the literature regarding the factors that can predict
resilience among young adults who were exposed to domestic violence.
Research showed that negative outcomes as a result of risk factors, such as
domestic violence, included self-harming tendencies, anger and frustrations, fighting,
alcohol and drug abuse, juvenile delinquency issues, suicide, depression, and spending
time in juvenile detention/treatment facilities (Beam, Gil-Rivas, Greenberger, & Chen,

4
2012; Plancherel & Bolognini, 2012; Storksen, Roysamb, Moum, & Tambs, 2010). Once
the individuals are removed from detrimental home situations, however, their resilience
may increase (Kassis, Artz, Moldenhauer, Geczy, & Rossiter, 2015). Potential factors
that may predict resilience development included age (Ali, Naylor, Croot, & O’Cathain,
2015; Garthe, Sullivan, & Kliewer, 2014; Jan et al., 2015); gender (Black et al., 2015;
Dietz et al., 2014); ethnicity (Danquah, Wasserman, Meininger, & Bergstrom, 2010;
Flores, Cicchetti, & Rogosch, 2014; Holland & Gill, 2010; McKnown-Johnson & Rhodes
2013; Zautra, Hall, & Murry, 2010); individual emotional and physical abilities
(Monique, 2015); types of exposures (Dawn & Lynda, 2015); frequency of domestic
violence exposure (Johnson & Easterling, 2015); and when the exposures occurrences
likely stopped by either removal from the social environment or by intervention agencies
or groups that intervened to assist the individual from further emotional and physical
harm from such violent environment (Fossie et al., 2016). Research regarding the
influence of domestic violence on resilience was conflicted, suggesting it might either
improve resilience (Anderson, Renner, & Danis, 2012) or lessen it (Kassis, Artz, &
Moldenhauer, 2013). Further research was required to understand whether and how the
variables in conjunction predict resilience among adolescents after being removed from
the domestic violence situation.
Problem Statement
Domestic Violence
Domestic violence affects many adolescents regardless of ethnicity, age, gender,
race, or socio-economic background (Hamberger, 1994; Monique, 2015). Recent reports

5
on the cause of family violence suggest that poor home management, economic situation,
unemployment, parental education, and relationship status contribute to domestic
violence (Bradley & Corwyn, 2002; Graham-Bermann, 1994). The effects may continue
into young adulthood, as Carlson (2000) and Widom and Wilson (2015) proposed that the
domestic violence cycle potentially perpetuates itself among prior victims. Specifically,
Storksen et al. (2005) found that as child develops within a domestic violence situation,
he or she will begin to see the abusive relationship between his/her parents and may
demonstrate emotional withdrawal. Storksen et al. reported that this developmental
problem may lead the child, and later the young adult, to engage in self-harming
behaviors, such as anger and frustration.
In the long term, domestic violence, particularly affects those exposed to domestic
violence within the adolescent stage of development. Adolescents who are exposed to
domestic violence are reported to have emotional and development deficits (Allen &
Allen, 2006; Carlson, 2003; Johnson & Easterling, 2015). According to Kupersmidt
(1998) and Olszewski-Kubilius, Young Lee, and Thomson (2014), the adolescent stage
has been characterized as the time for developing self-awareness and independence,
especially from age 10-17 years. Regardless of variable age differences, negative
interaction and poor bonding relationships between parents and the child aged 10-17
promotes poor cognition and mediated trauma, thereby hindering the ability to set goals
toward self-actualization (Maureen, Dawn, & Lynda, 2015; McElliskem, 2006).
Therefore, when domestic violence occurs, the child could get stuck without
improvements in maturation that may translate to their young adulthood. Moreover, when

6
the same child experiences threats, emotional instability, maltreatment, and neglect,
he/she may begin to use those aforementioned traumatic experiences to perpetrate
aggression, not typically correlated with the child’s age, gender, or ethnicity (Carlson,
2000; Johnson & Easterling, 2015). In sum, domestic violence experiences affect
children’s growth, delay age progression and maturation, create speech impairment, and
lead to poor resilience (Bliststein, 2005). These effects may have a long term effect,
which requires additional investigation of factors that might influence resilience among
young adults.
In prior research, age, gender, and culture have been preliminarily examined for
their effect on the extent of damage done by domestic violence. Grotberg (2010) posited
that in spite of age, culture, and gender differences, generally adolescents who are
exposed to domestic violence exhibit poor emotions, learning disabilities, self-harming,
low self-esteem, and aggression. They can also exhibit symptoms of chronic depression
and posttraumatic stress disorder (PTSD), leading to mental health disorders (Berk 2000;
Lanza & Taylor, 2010). However, individuals’ responses to external adversities may
differ slightly from each other given the individual’s age, culture, and gender (Fergus &
Zimmerman, 2005). These factors may influence why some young adults exposed to
domestic violence are more resilient than others (Fergus & Zimmerman, 2005). Kliewer
and Murrelle (2007) and Jan et al. (2015) proposed that adolescents’ cultural response to
domestic violence occurs in different emotional adjustments given their upbringing.
Therefore, domestic violence in general is a negative phenomenon on personal growth
regardless of gender, culture, and age (Berk 2000; Jan et al., 2015; Lanza & Taylor, 2010;

7
Whipps, 2009); however, environmental factors can determine the extent of these
developments.
Resilience
Within the field of psychology, resilience is presented as an individual’s ability to
cope with social, environmental stress in spite of adversity (Lanza & Taylor, 2010;
Ungar, 2004a). Resilience research has gained much attention among scholars despite
differing opinions that resilience can be based on individual’s temperament and family
upbringing (Margolin & Gordis, 2000; Olszewski-Kubilius et al., 2014). Within the
treatment facility setting, studies have shown that adolescents have the ability to cope
with external predicaments that can be incorporated in therapy (Ali et al., 2015; Masten,
2009). Masten (2001) proposed that “programs will be most effective when they tap into
these basic but powerful systems” (p. 235), yet current models of resilience continue to
be contested in the literature (Ungar, Ghazinour, & Richter, 2013).
Adolescence is considered the most vulnerable stage for the development of
resilience (Margolin & Gordis, 2000). Fergus and Zimmerman (2005) reported that
adolescents’ resilience development is achieved when the treatment plan is focused on
strength-based treatment, wherein the therapist investigates areas of focus for particular
individuals. This strength-based criterion should also consider the individual’s age,
gender, and culture to achieve a positive therapeutic outcome as these can be reinforced
through positive interactions and rapport with the practitioner or therapist (Fergus &
Zimmerman, 2005). A predictive model for resilience would help to inform such
intervention for individuals previously exposed to domestic violence.

8
Domestic Violence Treatment and Resilience
Unfortunately, the strength-based focus of research has not yet reached treatment
for victims of domestic violence. This is a problem in both protective supervision and
among the general population. According to the Child Welfare System (2011), a large
number of American minors under protective supervision are domestic violence victims,
yet many studies do not attempt to determine whether and how resilience is developed for
these victims, and if demographic variables might influence the development of
protective factors and resilience. In other populations, researchers have determined that
exposure to domestic violence increased resilience (Anderson et al., 2012). In addition,
demographic factors that may influence resilience development included age (Ali et al.,
2015; Garthe et al., 2014; Jan et al., 2015); gender (Black et al., 2015; Dietz et al., 2014);
and ethnicity (Danquah et al., 2010; Flores et al., 2014; Holland & Gill, 2010;
McKnown-Johnson & Rhodes 2013; Zautra et al., 2010). It is not known whether and
how the variables in conjunction predict resilience among young adults after being
removed from the domestic violence situation.
The discussion of factors influencing resilience among young adults exposed to
domestic violence is essential because Family and Youth Protective Services, Youth
Probation Departments, and the Juvenile Courts have traditionally responded to
adolescent victims by providing crisis intervention programs (Flores et al., 2014).
However, lack of current research data describing the factors that predict the
development of resilience among young adults who were victims of domestic violence
results in little or no information to generate appropriate treatment programs that will

9
help victims set personal goals for the future. Based on these issues, a significant gap
existed in the literature concerning the variables that influence the development of
resilience among young adults.
Purpose of the Study
The purpose of this quantitative study was to examine whether domestic violence,
age, gender, ethnicity, individual emotional and physical abilities, types of domestic
violence exposure, and frequency of domestic violence exposure can adequately predict
resilience among young adults in the Midsouth region of the United States. Resilience,
the criterion variable, was defined as the individual’s ability to bounce back and set
personal goals for future functioning. In this study, I applied Bronfrenbrenner’s
ecological systems theory to examine domestic violence predictor variables experienced
in the mesosystem (home) in the population. The criterion and predictor variables in this
study were: (a) resilience (criterion variable), (b) domestic violence, (c) age, (d), gender,
(e) ethnicity, (f) individual emotional and physical abilities, (g) types of domestic
violence exposure, and (h) frequency of domestic violence exposure based on
individual’s exposure experiences.
I aimed to create an initial, exploratory, predictive model for resilience among
young adults based on variables including exposure to domestic violence, age, gender,
ethnicity, individual emotional and physical abilities, types of domestic violence
exposure, and frequency of domestic violence exposure. The results provided from this
study were expected to enhance understanding of the demographic factors that influence
adolescents’ behavioral responses and be used to devise appropriate treatment plans that

10
will help adolescents recover from poor home environment experiences (see Garthe et al.,
2014). While not a focused purpose of this study, the results may potentially provide a
rationale for improved treatment methodologies among young adults.
Research Question and Hypotheses
I developed the following research question to guides this study:
Do domestic violence, age, gender, ethnicity, individual emotional and physical
abilities, types of domestic violence exposure, and frequency of domestic violence
exposure, when in linear combination, significantly predicts resilience as
measured by the Resilience Scale among young adults in the Midsouth region of
the United States?
H
0
: Domestic violence, age, gender, ethnicity, individual emotional and
physical abilities, types of domestic violence exposure, and frequency of
domestic violence exposure, when in linear combination, do not
significantly predict resilience as measured by the Resilience Scale among
young adults in the Midsouth region of the United States.
H
1
: Domestic violence, age, gender, ethnicity, individual emotional and
physical abilities, types of domestic violence exposure, and frequency of
domestic violence exposure, when in linear combination, significantly
predicts resilience as measured by the Resilience Scale among young
adults in the Midsouth region of the United States.

11
Theoretical Framework
The theoretical framework for this study was the socioecological theory advanced
by Bronfrenbrenner (see Bradley & Corwyn, 2002; Gunlicks-Stoessel, Mufson, Jekal, &
Turner, 2010), which looks at an individual’s development within the context of the
system of relationships that form behaviors within an individual’s environment. Key
concepts of this theory include microsystem, mesosystem, and exosystem (Bradley &
Corwin, 2002). To study a person’s developmental process, not only the immediate
environment (mesosystem) but also the larger environmental interactions (exosystem) are
investigated (Gunlicks-Stoessel et al., 2010).
Bronfenbrenner’s theory posits that complex layers of a social environment affect
developmental responses and behaviors (Bliststein, 2005; Bornstein, Hahn, & Haynes,
2010). This assertion infers that the interaction between factors in the person’s biological
stages (microsystem), the immediate family/community environment (mesosystem), and
the societal landscape can trigger certain developmental issues (exosystem). In this study,
I expected that the social environment mesosystem (IV), characterized by (a) exposure to
violence and (b) the individual’s age, gender, and ethnicity, would influence resilience
(domestic violence). For example, studies utilizing Bronfenbrenner’s model, including
Archer and Brown (1988); Bornstein et al. (2010); Garthe et al., (2014); Carlson (2000,
2003); and Middlebrooks and Audage (2008) reported that (a) witnessing poor parental
modeling; (b) witnessing family altercations such as physical fights, arguments and
name-calling between family members; and (c) parents choosing a lover over the children
in the home can become onset for low self-esteem, emotional neglect, maltreatment,

12
physical abuse, emotional abuse, and aggression. Thus, I used the following key
variables: exposure to domestic violence, age, gender, ethnicity, individual emotional and
physical abilities, types of domestic violence exposure, and frequency of domestic
violence exposure to determine young adults’ ability to predict resilience in this study.
Nature of the Study
In this study, I used a quantitative methodology based on postpositive worldviews
that suggest objective and measurable outcomes, which are required to advance
knowledge (Creswell, 2009; Dietz et al., 2014) and test hypotheses. A step-wise multiple
linear regression design was employed. A multiple linear regression is appropriate for
analysis of joint and separate influences of two or more predictor variables on the
criterion variable, generating a linear equation (Dietz et al., 2014). The linear model
produces a standardized regression coefficient, indicating the relative importance of the
corresponding predictor variables to determine the predicted value of the criterion
variable (Dietz et al., 2014). Multiple linear regression was appropriate because I sought
to predict a quantitative outcome variable (resilience) or criterion variable based on
several potentially predictive independent or predictor variables. The step-wise method
for inserting the variables into the equation was used in order to create a reduced
predictive model that uses only the significant variables.
I drew the sample of young adults included in this study from mentees in the Big
Brother Big Sister (BBBS) community organization in the Midsouth region of the United
States. The BBBS organization connects children and young adults with mentors from
around the county to help them become motivated to self-actualize (BBBS, 2017). This

13
program accepts children and young adults aged 10 to 26 years from the general
population, although this study only included young adults who were between the ages of
18 and 25. Selecting eligible participants from BBBS helped ensure variability in the
criterion variable, resilience, and resulted in a more accurate predictive equation.
The variables that I investigated as potential predictors of resilience included
exposure to domestic violence, age, gender, ethnicity, individual emotional and physical
abilities, types of domestic violence exposure, and frequency of domestic violence
exposure. Resilience was measured by the Resilience Scale, developed by Wagnild and
Young (1993). Exposure to domestic violence, individual emotional and physical
abilities, types of domestic violence exposure, and frequency of domestic violence
exposure were measured using the Children’s Exposure to Domestic Violence (CEDV)
instrument (Edleson et al., 2007; Margolin & Gordis, 2000; Tilton-Weaver, 2014). The
variables of age, gender, and ethnicity were assessed using a demographic questionnaire.
In this study, I used the term other in association with the variable of culture, the
participants' self-identified culture groups. Some participants may not have considered
themselves members of any of the ethnic groups listed on the questionnaire. Another may
have also been selected by respondents who viewed themselves as mixed race.
Definitions
The main operational definitions required for this study include: adolescence,
domestic violence, adolescents’ aggression, resilience, age, culture, gender, and ethnicity.
The definitions of these terms are as follows:

14
Age: Part of the duration of an organism or a thing between the beginnings of a
being at any given time aiming at maturation (Bogat, Levendosky, & von Eye, 2005;
Hankin & Mermelstein, 2010).
Aggression: A behavior derived from accumulated violent observations that defile
resilience, leading to frustration as a method of responding to threats (Jacobson &
Mufson, 2010; Whipps, 2009). According to Lippold, Greenberg, and Collins (2013),
aggression is an obstructive behavior “displayed by self-expressive drive to mastery” (p.
156).
Domestic violence: A pattern of behavior by a family member to intimidate, harm,
or dominate their victims (Dutton, 1994; Henrichs, Bogaerts, Sijtsema, & Van Mierlo,
2015).
Ethnicity: The individual’s identity and awareness of belonging to a particular
cultural group (Dietz et al., 2014). This distinction enables an individual to maintain
identity and the characteristics of that group (Black et al., 2015; Buka, Stichik,
Birdthishtle, & Earls, 2001).
Gender: Beyond biological differences, gender develops self-identity depending
on designations of male/female and influences an individual’s ability to respond to the
environmental issues based on society’s expectations (Black et al., 2015; Bradley &
Corwyn, 2002).
Resilience: The strength-based approach or the ability to bounce back and take
control of an individual’s destiny (Jaffee, Caspi, Moffitt, Polo-Tomas, & Taylor, 2007).

15
Assumptions
I assumed that resilience is a normal function of human experience, wherein
humans adapt particular strategies to cope with “serious threats to adaptation or
development” (see Greenberg, and Collins, 2013; Masten, 2001, p. 228). Therefore, I
assumed that developing a predictive model for resilience was potentially useful for
treatment of young adults who have been exposed to adverse situations to determine the
extent of development in resilience that is required for particular young adults. I also
assumed that appropriate screening of young adults’ experiences in home violence was
necessary to obtain information on the individual’s strength and weakness (Bradley &
Corwyn, 2002; Henrichs et al., 2015). To ascertain the family dynamics, I proposed that
an analysis would reveal the young adults’ involvement in domestic violence and in the
process facilitates placement (see Delfos, 2003; Kernberg, Ritvo, & Keable, 2012).
Lastly, I assumed if the local agencies and administrators understand the impacts of an
individual’s home experiences of the individual’s story, this consideration would
minimize behavioral reenactment and eliminate future recidivism because of resilience
development. These assumptions were verified by surveying young adults in BBBS in the
southwest region of Texas.
Scope, Limitations, and Delimitations
Scope
I designed this study to explore whether or not selected predictor variables can
adequately predict resiliency among young adults. Specifically, I focused on developing a
predictive model to explore the predictive relationship between young adults’ resilience

16
and several potential predictive variables: (a) domestic violence; (b) age; (c) gender and
ethnicity; (d) individual emotional and physical abilities (Monique, 2015); (e) types of
exposures (Dawn & Lynda, 2015); and (f) frequency of domestic violence exposure
(Johnson & Easterling, 2015). In this study, I constructed a variable-focused model of
resilience, rather than the person-focused model (Black et al., 2015; Masten, 2001). The
outcome of this process established a predictive model for resilience which may be useful
for increasing the efficacy of treatment based on the individual’s history of domestic
violence, age, gender, and ethnicity.
Limitations and Delimitations
The main limitation of this study was the small sample size of young adults drawn
from within a limited geographic region. The population and resulting sample resides in
the Midsouth region of the United States and does not represent the population impacted
by domestic violence in other regions of the country. Consequently, the results obtained
from this study may not be used to generalize the U.S. population and only to the
Midsouth region. Additionally, the study population consisted of Hispanic, African
American, and Caucasian young adults. Also included in the study are some participants
who may not have wanted to identify themselves as members of a particular race or are
neutral in terms of their racial identity. Therefore, it was appropriate to include other as
an option on the questionnaire. Despite these limitations, I expected that the results could
benefit organizations in other regions of the United States who are also working with
young adults affected by domestic violence.

17
Significance
Significance for Researchers
The significance of this study was based in potentially developing a predictive
model for resiliency by examining exposure to domestic violence, age, gender, ethnicity,
individual emotional and physical abilities, types of domestic violence exposure, and
frequency of domestic violence exposure among young adults. Previous studies of
resilience have produced contradictory results of resilience prediction, and no resilience
studies have focused specifically on young adults exposed to domestic violence after they
have been removed from the domestic violence situation (Kassis et al., 2013; Masten,
2001; Van Wyk, 2011). This study may represent a turn to an asset-based domestic
violence research, wherein researchers emphasize potential assets that young adults
exposed to domestic violence develop. This change in domestic violence research would
be consistent with the asset-based approach in resilience research (Damant et al., 2010;
DeForge, Belcher, O’Rourke & Lindsey, 2005; D’Imperio et al., 2000; Resnick,
Bearman, Blum, & Bauman, 1997; Rutter, 1985).
Significance for Practice
Developing a predictive resilience model can have beneficial effects for treatment
of individuals affected by domestic violence (Hopf, 2010). It is imperative to provide
education on the issues affecting young adults’ coping skills and resilience formation.
The awareness I attempted to develop in this study will make way for social justice
advocates in the best interest of adolescents who have been victims of domestic violence.
The development of awareness will also promote plans for appropriate psychological

18
evaluation based on young adults’ perception of values and worldviews for their
behaviors before placed in state or private treatment facilities. These suggestions are
significant for therapists and direct care-workers who desire, awareness of young adults’
ordeals in order to acquire therapeutic tools for individual resilience formation (Delfos,
2003; Mowder, Cummings, & McKinney, 2010).
Significance for Social Change
The first step toward social change as a result of this study is the potential
contribution this research may provide in illuminating factors that potentially predict
resiliency among young adults. This new knowledge may assist treatment providers in
determining the potential negative effects of domestic violence and provide a first step in
understanding how to treat adolescents exposed to domestic violence. The project also
was a part of integrating domestic violence awareness within the treatment community.
The outcome could help intake departments, therapists, direct-care workers, and facility
administrators make appropriate assessments of each individual who is a victim of
domestic violence and the impacts this home situation has created on young adults’
resilience response.
When therapists and direct care workers do not understand the individual’s
experiences and worldviews, young adults are likely to be judged based on the presented
behaviors (Daro, 1988). Such harsh judgment, not only delays the implementation of
treatment plans, but also triggers anger, self-defense, aggression, and loss of hope for
resilience (Prince-Embury & Steer, 2010). Therefore, to create social change, community
leaders, including practitioners such as therapists, Child Protective Services, and

19
treatment facilities, need to collaborate and organize treatment plans based on the
individual needs which consider age, culture, ethnicity, and gender (Daro, 1988; Prince-
Embury & Steer, 2010). This process would help therapists and stakeholders understand
the individuals’ emotions and psychological needs of the individual family member
temperaments (Delfos, 2010). When these key issues are in place, a collaborative effort
between the community leaders and policy makers will become consistent to advocate for
social change in the best interest of these young adults in the community (Gelles, 1997;
Wardle, 1999).
Summary
In this chapter, I proposed that domestic violence is a multifaceted issue that
cannot be easily resolved due to the field’s misconception of ideas and lack of forensic
exploration of the cause due to outdated literature. I also stated that poor home
environments and demographic factors may influence resilience development. Therefore,
I undertook a study that would attempt to create a predictive model for resilience
development as experienced by a sample of young adults. In order to understand the
phenomenon, I examined Bronfrenbrenner’s ecological systems theory, which explains
the relationship between domestic violence experienced in the mesosystem (home) and
its effect on young adults’ emotional development (Bureau, 2009; Edleson et al., 2007;
Edleson, Shin & Armendariz, 2008; Kleinman, Adams, Kashdan, & Riskind, 2013). If a
predictive model is developed, it could have broad significance among policy makers,
therapists, and stakeholders in the region as inevitable tasks, to implement guidance that
will effect changes in placement procedures that aim to eliminate poor resilience. In

20
Chapter 2, I will provide a literature review and more detailed information on the social
and psychological constructs underlying this study.

21
Chapter 2: Literature Review
Introduction
The purpose of this quantitative study was to examine whether domestic violence,
age, gender, ethnicity, individual emotional and physical abilities, types of domestic
violence exposure, and frequency of domestic violence exposure can adequately predict
resilience among young adults in the Midsouth region of the United States. In this
chapter, I will examine the influence of an individual’s age, gender, and ethnicity on
domestic violence among young adults in the Midsouth region of the United States.
Through the literature review, I clarify the gap that necessitated this research.
The databases I used in this study included: ERIC, EBSCOhost, PsychINFO,
Mental Measurement Yearbook database, and Academic Search Premier. I accessed these
databases through the online library of Walden University. Other literature I used in this
study included published books and scholarly journal articles to explore the impact of
domestic violence on adolescents’ resilience responses. In this study, I examined some
key topics relevant to this topic: (a) the theoretical framework of Bronfenbrenner’s theory
and nature vs. nurture; (b) an overview of domestic violence, adolescents, and the social
environment; (c) domestic violence impacts on adolescents; (d) resilience overview; (e)
adolescents’ resilience adaptation; and (f) factors that promote resilience.
Theoretical Framework: Bronfenbrenner’s Theory
Bronfenbrenner’s (2009) theory investigated the development of a person who
develops behavioral responses to relationships and context within a social environment.
Bronfenbrenner proposed that complex layers within social environment can affect age

22
and gender developmental processes as well as behavioral responses despite an
individual’s ethnicity (see Berk, 2000; Lanza & Taylor, 2010). Researchers indicated that
the environment not only contributes to a child’s behavior, but also affects the bioecology
that aids in successful child development (Children’s Health Fund, 2011; Ekstrom &
Young, 2009). In the theory of the bioecological system, Bronfenbrenner posited that
interaction between immediate families, the environment, and human biology are
landscapes for human development (Ekstrom & Young, 2009). Thus, child development
should not be limited to biological trends alone, but should also include the immediate
environment and the child’s interaction within the larger system that forms the
individual’s attitude and behaviors (Addison, 2008; Edwall, 2012). The layers of
interaction that form a child’s behavioral responses, according to Bronfenbrenner (2009)
included the microsystem, the mesosystem, the exosystem, and the chronosystem.
Microsystem
For Bronfenbrenner, a microsystem is one of the layers that creates a person’s
structured interaction with the immediate environment and conditions the individual’s
behaviors (Berk, 2000; Hjemdal, Vogel, Solem, Hagen, & Stiles, 2011). As the individual
develops interaction within the system, complex alliances are formed with the multiple
presences of outside groups, such as peers, extended-family, neighborhood, church,
school, or the childcare environments (Bronfenbrenner, 2009). These outside stimuli
result in dual means of interaction (Bronfenbrenner, 2009). Bronfenbrenner examined
these two types of interaction and classified them as (a) from the child and (b) toward the
child systems of interaction (Berk, 2007). The from the child scenario exists when a

23
child’s behavior, not meeting family, cultural expectations, causes friction in the home
(Edwall, 2012). For example, a child may use certain words or responses that are
inappropriate to the values. On the other hand, a toward the child scenario is when the
child’s behaviors initiate parents’ consequences of such behaviors (Berk, 2007; Edwall,
2012; Walker, Kerns, Lyon, Bruns, & Cosgrove, 2010). The consequences lead the child
to question their cultural difference to peers, a frustration that may result in negative
responses towards others. This bidirectional influence, according to Bronfenbrenner
(2009), shows how the environment interaction can quickly condition a child’s response
toward others with whom he/she comes in contact.
Mesosystem
The mesosystem is the trust-building structured interaction, connecting the child
and outer groups (Berk, 2000). Teachers, schools, churches, and neighborhoods condition
a child to build trust and develop resilience, and the absence of this structured system can
cause a delay in the development of these behaviors (Ungar, 2011). Ungar’s (2011) study
also revealed that environmental connections affect adolescents and may condition
adolescents to the external stimuli, responses because they are aware of the repeated
accounts of specific violence surrounding their social environment to which the exposure
to those violence exposures could trigger violence responses. Development theorists
assert that as adolescents become used to making their own decisions, community
mentors and parental relationships teach the skills needed to master life challenges
against adversity (Bornstein et al., 2010; Solberg, Carlstrom, Howard, & Jones, 2007).
Bronfenbrenner confirmed adolescents’ connections between positive mentors and

24
parental bonding relationships, promote motivation toward resilience adaptation (Hurt,
Malmud, Brodsky, & Giannetta, 2001).
Arundale (2004), Hurt et al. (2001), and Wan-Yi (2010) confirmed that higher
rates of co-occurrence between interfamilial and community violence exposure does
eventually exist in most of the adolescent’s environment, following Bronfenbrenner’s
theory; however, positive mentors and parents’ bonding relationships can generate
positive interactions that replace negative experiences and support adolescents’ self-
actualization. Rossman, Hughes, and Rosenberg (2000) and Garthe et al. (2014) clarified
that poor environmental connections not only expose adolescents’ to develop high risks
behavior, but also compromise the individual’s resilience efforts generated by lack of
trust for establishing relationships with others. Therefore, poor environmental
experiences, whether within the family or community, have equal negative effects on
adolescents’ moral life development (Patterson, 2002; Wan-Yi, 2010). In summary,
adolescents’ positive interaction with adults in the family or within the social
environment motivates adolescents to establish trust, positive thinking, and
empowerment to negate resentment for aggression.
Exosystem
The exosystem is the layer of interaction involved in a child’s failure to function
directly or participate actively in the daily decision-making process (Patterson, 2002;
Wan-Yi, 2010). The child’s isolation creates resentment, anger, and despair, all of which
make the child act out without giving second thoughts for his/her actions (Patterson,
2002). When a child is left out or forced to comply with family dictating the child’s

25
emotional cultivation, he/she may not assume responsibilities appropriately (Berk, 2000;
Goodrum, Jones, Kincaid, Cuellar, & Parent, 2012). Additionally, leaving a child out of
important decision-making processes may result in negative behaviors (Berk, 2000). For
example, a community-based or family issue where a child is denied a voice can become
grounds to feel out of control of his or her environment, which could trigger low self-
esteem, disconnection, impaired thinking, and poor goal setting.
On the other hand, according to Kaufman et al. (2000) when a child is included in
the family discussion of decisions, the child feels empowered to establish relationships
with the environment instead of living in isolation—which sends negative messages that
the environment is unsafe. Consequently, the child’s thinking ability is suppressed and
repressed, resulting in impulsivity, hyperactivity, and aggression (Kaufman et al., 2000).
The child’s id-ego and superego-ego build defense mechanisms against the social system
(Johnson et al., 2002).
Chronosystem
Bronfenbrenner’s chronosystem refers to interaction changes that occur within a
child’s social system (Larson & McQuiston, 2011). Bronfenbrenner explained that the
child’s environment encompasses the dimension of time and experiences for responses
and suggests that environmental development crisis inevitably and frequently occurs
(Garthe et al., 2014; Henderson, 1995). For example, parents fighting, separation, and
divorce are emotional conflicts that could impair a child’s developmental process to
exhibit anger, frustration, blame, low self- esteem, and poor resilience into adulthood
functioning (De Los Reyes, Thomas, Goodman, & Kundey, 2013; Pinel, 2003). However,

26
as the child becomes older, he/she will begin to process how the environmental changes
may influence his/her future functioning (Carlson, 2003; Gunlicks-Stoessel et al., 2010)
and correlated aggressors.
In summary, Bronfenbrenner’s theory presents the five systems of interaction to
explain the challenges in a child’s development and its potential impacts on emotional
functioning that could become a nursing ground for domestic violence. Therefore, I used
the Bronfenbrenner’s theory as the theoretical framework that provides explanatory value
for this study. Another important influence of Bronfenbrenner’s theory was drawn from
the combination of the simultaneous influences of biological factors (nature) and
environmental factors (nurture).
Nature vs. Nurture
In the field of psychology, the concept of nature vs. nurture is one of the terms
used extensively in child maturation dimensions (Dietz et al., 2014; Zuckerbrot, Cheung,
Jenson, & Stein, 2007;). Bronfenbrenner’s (2009) theory indicated that environmental
effect and genetics are the component parts from which a child could derive a sustaining
system for development, and both genetics and environment can trigger an individual’s
emotional responses (Berk, 2000, 2007; Goodrum et al., 2012). While the chronosystem
examines the role of environment and the dimension of time relating to a child’s
experiences in the social system (Feldman, 2003; Gunlicks-Stoessel et al., 2010), genetic
researchers contend that biology and the social environment impact human emotional
development. According to Jacobson and Mufson (2010), and Ridley (2003), a child’s

27
biological and social environment play significant roles in the child’s ongoing emotional
development.
Bronfenbrenner argued that in spite of human biology, the interaction between a
child and the social environments can become complex (Berk, 2000, 2007; Sorbello,
Eccleston, Ward & Jones, 2012), thereby resulting in varied responses. Given the nature
of poor environmental nurturing, Bronfenbrenner proposed that when a child grows up in
a violent environment, delinquency is inevitable. Other researchers indicated that as a
result of a violent environment, poor behavioral choices and other psychopathological
dilemma will begin to unfold (Plomin & Spinath, 2004; Williams & Steinberg, 2011).
In summary, the social environment and human biology can trigger certain
behavioral responses, particularly when those experiences are particularly traumatic, as is
the case in domestic violence scenarios. Certainly, parents or adult role modeling are
instruments for redirection that would affect future functioning in spite of vulnerability,
helplessness, and hopelessness of experiences. However, this modeling may not be
available for those children who are exposed to domestic violence, such as the
participants I examined in this study.
Overview of Domestic Violence
Domestic violence has many different names: family violence, intimate partner
abuse, wife beating, battering, child abuse, or family member abuse (Kumar, Steer, &
Gulab, 2010; Rodriguez, Bauer, McLoughlin, & Grumbach, 1999; Straus & Smith,
1999). According to the American Psychiatric Association (APA; 2008), violent acts
toward other family members can result in physical, emotional, and psychological

28
consequences, especially in adolescent children living in the home. Although current and
former intimate partners perpetrate many incidences of domestic violence, there is no
“typical” victim—it is prevalent in all socioeconomic families, regardless of gender and
with no specific cultural limitation (Bureau, 2009; Prince-Embury, 2010; Rodriguez et
al., 1999). In many reported domestic violence incidences, adolescents, children, and
female partners are more likely to experience bodily injuries, self-harming, and other
psychological and emotional hurt (Carlson, 2000; Rodriguez et al., 1999). Over time,
cognitive impairment among abused adolescents has increased, evidenced in multiple
studies on early childhood trauma and in the intrafamiliar violent exposures (Bureau,
2009; Margolin & Gordis, 2000; Straus, Gelles, & Steinmetz, 1980; Tilton-Weaver,
2014).
The experiences of domestic violence and abuse differ for different couples, but
there are some similarities in the experience, according to the research. In abusive
situations, domestic abuse often occurs between partners after arguments become hostile
(APA, 2008; Lippold, Reenberg, & Collins, 2013). In these instances, physical abuse is
as a result of poor impulse control includes punching, slapping, pushing, choking, or
bodily injury on the victim that could lead to physical and emotional pain (Tilton-
Weaver, 2014). Alternatively, some abusers only engage in verbal assaults. Thompson,
Saltzman, and Johnson (2003) reported that verbal assault causes more mental and
emotional damages as opposed to physical assault, which causes physical harm. Although
verbal attacks may not leave physical marks, they may result in feelings of inadequacy,
low self-esteem, and later, aggression for self-defense (Thompson et al., 2003). It is also

29
noteworthy that when a partner abuses a parent, the child is emotionally affected (Boydell
& Ferguson, 2012; Thompson et al., 2003). The consequence may be that the child will
use the learned behavior to develop social responses and other psychopathology against
the associated environment. These secondary effects are troubling due to the prevalence
of domestic violence; I will review these effects in the next section.
Domestic Violence Statistics
Researchers estimated that approximately 14 million American adolescents are
affected by domestic violence annually, and over 3.3 million of adolescents have
witnessed violence in their homes each year (APA, 2008; Bureau, 2010; Thompson et al.,
2003). These numbers were derived from national surveys, which were not designed to
measure individual adolescent’s age, ethnicity, and gender for resilience. Kaufman et al.
(2000), Thrash, Cassidy, Maruskin, and Elliot (2010) and Thompson et al. (2003)
reported that 33.2% of Canadian and 40.2% of U.S. adolescents have witnessed multiple
domestic violence events in their own homes; unfortunately, the estimate again did not
report types of exposure. The oversights and gaps in the domestic violence statistics have
limited the field’s understanding of domestic violence’s impact. Perhaps resulting from
this lack of awareness, the U.S. Census Bureau’s recent poll estimated that domestic
violence has increased from 10% to 30% over the past 50 years from 1951 through 2010
(Allen & Allen, 2000; U.S. Census Bureau, 2010).
It is interesting to note that the effect of adolescents’ exposure to domestic
violence not only affects the lives and responsorial behaviors of adolescents who are
abused, but also impacts the negative development upon which they express emotions in

30
their future functioning. According to Graham-Bermann and Edleson (2001), it is
estimated that approximately 10 million adolescents are more likely to be exposed and or
witnessing domestic violent acts each year. Prior studies documented the negative long-
term effects of adolescent exposure to domestic violence which is carried on to adulthood
development, thereby causing certain emotional deficits in terms of making personal
decisions in preparation for transition to adulthood life (Fodor, 2010; O’Shea, Spence, &
Donovan, 2013). Although prior research has also stated that not all adolescents exposed
to domestic violence have the tendency to become aggressive or non resilient, however,
the study mentioned some of the deficits that might occur whether the individual is
resilient or not. These effects include but not limited to self-blame, shame, low self-
esteem, anxiety, depression, and PTSD. Giving these effects as maturity continues, it is
also very important to know that adolescents may also exhibit significant anger emotions
as well as behavioral, cognitive, and social problems (Evans, Davies, & DiLillo, 2008;
Fowler & Chanmugam, 2007). In addition to these symptoms and characteristics in
behavioral responses, it is also reported that adolescents living in homes where domestic
violence is frequently observed have a greater risk of becoming abuse themselves in part
because the observed behavior often and always dictates the individual information
processing, cognition, and the physical abilities associated with internal locus of control
to respond to the external stimuli.
Contextual Emphasis in the Associations Between Domestic Violence and Early
Adulthood Mental Health

31
The current consensus among researchers is that individual’s responses to
domestic violence exposure may differ from each other (Fergusson et al., 2005). It has
also been reported that exposure to domestic violence associated with increased rate of
significant symptoms of fear, self-blame, speech deficits, anger emotions, anxiety, and
depression for the witness victims (Gao et al., 2010; Lindhorst & Beadnell, 2011; Straus
& Mickey, 2012). However, the frequency and severity of the exposure is also significant
as its negative consequences may as well depend upon the extent to which the victimized
parent expresses the aftermath effects of the event such as symptoms of depression and
anxiety and also whether or not the parent has coping skills and or supported by other
family members or even the children in the home (Howell, 2011; Renner & Boel-Studt,
2013). Holmes (2011) used secondary data analysis from the National Survey of Child
and Adolescent Well-Being (NSCAW) to determine that domestic violence witnessed
between parents associated significantly especially with poor mental health outcomes.
Holmes further suggested that major depressive episodes, heavy alcohol use, and other
substance abusive related behaviors may affect the coping skills of children and
adolescents aggressive behavior in the long term (Blackwell et al., 2015; Lang,
Blackwell, Harmer, Davison, & Holmes, 2012; Marshalll, Tilton-Weaver, & Stattin,
2013). Moreover, coping activities on the part of parents in domestic violence situations
such as smoking, partying, and children abandonment can also associate with children
and adolescents externalizing and internalizing problems that can be carried on to
adulthood even after controlling for numerous covariates (Ashford, van Lier,

32
Timmermans, Cuijpers, & Koot, 2008; Graham-Bermann & Edleson, 2001; MacMillan &
Wathen, 2014; Tjaden & Thoennes, 2014).
Although a significant direct association exists between parent’s exposure to
domestic violence and the impacts it creates in children and adolescents’ emotional
responses and behavioral distress (Yoo & Huang, 2012 ), it is also worthy to note that the
effect of domestic violence on children and adolescents may emerge in poor physical
abilities associated with helplessness and hopelessness mediated by parental poor coping
skills/distress (Renner & Boel-Studt, 2013 ), substance abuse (Skeer, McCormick,
Normand, Buka, & Gilman, 2009; Skeer et al., 2011 ), family dynamics and structures,
and low income (Turner, Finkelhor, Hamby, & Shattuck, 2013). All of these factors may
contribute to the type of resiliency children and adolescent may display as maturity
progresses. However, no study existed that conjoined the confluence of variables,
including exposure to domestic violence, age, gender, ethnicity, individual emotional and
physical abilities, types of domestic violence exposure, and frequency of domestic
violence exposure, that might contribute to or detract from resilience.
There is yet to be disclosed in previous studies the form of analysis by
incorporating scientific sound data to promulgate evidenced based detail findings in
regards to this social phenomenon (Howell, 2011). This is because most studies used
cross-sectional rather than longitudinal formation of research, which makes it very
difficult to adequately control the range of potential emphasis in relating to the public
their outcome assessment to help treatment facilities who work with this population to
draft the appropriate treatment plan based on the individual young adults experiences

33
growing up in the violent homes. As a result, there are needs among scholars to plunge
into research in this area with prepared motivation to help the communities, society, law
makers, and treatment facilities to determine young adults’ behavioral issues and also to
ascertain whether within this population if gender differences impacts way they respond
to domestic violence also become aware of the percentile rate among those who may
perceive themselves as resilient (Halford, Farrugia, Lizzio, & Wilson, 2010; MacMillan
& Wathen, 2014).
According to Feder and MacMillan (2012), Halford et al. (2010), MacMillan and
Wathen (2014) and Tjaden and Thoennes (2000), the comorbid rate of adolescents home
violence exposure is between 45 and 70% giving the percentile rate of the survey
collected from a national database in 2009. These bodies of studies have reported
substantial negative impacts that this type of exposure contributes to individual responses
to domestic violence in adolescents in preparation to transition to adulthood. In spite of
this body of literature, several gaps in these research literatures require significant
attention to address the cultural implications that influence how the individuals may
respond to this social phenomenon.
Second, the studies conducted in this area concentrated on adolescents still living
with their mothers in battered women’s shelters (Gilbert, El-Bassel, Chang, Wu, & Roy,
2012). Researchers have also failed to obtain information from adolescent who have been
considered as runaway children and are left to fetch on their own exposing them to re-
victimization. Thus, I sought to gather information to analyze young adults in response to
their domestic violence experiences and the impact of these experiences in their

34
responses to the external stimuli and their quest to emotional transition to adulthood. I
believe this formation in the present study will clarify the ongoing effects of domestic
violence on adolescent transition to adulthood. It is the intention of this study to identify
the effects of domestic violence on adolescents with respect to the relationship with
resilience. Lastly, the present study examines whether exposure to domestic violence,
community violence exposure and substance abuse have differential effects on how
young adults perceive themselves as resilient in their transition to adulthood.
According to Carlson (2004), over 4 million adolescents living in violent homes
have experienced physical and emotional abuse, leaving children with emotional scars
that more often resulted in aggressive behaviors than resilience. In the late 90s, studies
mentioned the impacts of environmental exposure on adolescents’ violence (Polivka,
Lovell, & Smith, 1998). It was confirmed by the 1999 National Child Abuse and Neglect
Data Systems (1999) that approximately 826,000 children (12 out of every 1,000) are
victims of family and community violence. These environmental influences may lead to
problematic adolescent behaviors due to low resilience or the lack thereof (Lee, Hankin
& Mermelstein, 2010; Patterson, 2002). The relation between these factors stems from
the Bronfenbrenner’s theory of the microsystem, which revealed that poor behaviors are
consequences of harsh environments, as they lead to poor decision-making to compensate
for hurtful feelings and anger against the authority figures. The section below examines
the influence of domestic violence on adolescents.

35
Domestic Violence’s Impact on Young Adults
According to Bronfrenbrenner’s ecological system, human behavior centers on
environmental impacts that generate responses (Underwood, Tallbott, Mosholder & von
Dresen, 2008). Multiple studies of youth within residential facility schools found that
behavioral responses combined with family violence histories preclude physical,
emotional, and sexual abuse (Underwood et al., 2008) and other psychiatric issues
(O’Donohue & Ferguson, 2006). However, Fodor (2010), O’Shea, Spence, and Donovan
(2013), and Thompson et al. (2003) noted environmental upbringing may link to different
emotional responses. Domestic violence may have cognitive, emotional, behavioral, and
social effects on young adults.
Cognitive Effects
Young adults exposed to violence are potentially prone to experience life-trauma
followed by vulnerability, helplessness, extreme hopelessness, and self-worthlessness
(Clauzade, 2009; Sorbello, Eccleston, Ward, & Jones, 2012). Consequently, poor
cognition has been reported as a predominant issue among adolescents exposed to
domestic violence with little or no self-control. According to Pervin and John (2001) and
Ridley (2003), parent-to-child violence was associated with chronic abuse, maltreatment,
cognitive deficits such as low IQ, poor oratory skills, poor nutrition, attention, poor
memory, poor visual-motor integration skills and resilience deficit. A number of studies
reported that adolescents’ poor cognitive skills linked to truancy, poor academic, peer
pressure, aggression, and low self-esteem associated with poor home upbringing (Hurt et
al., 2001; Kliewer & Murrelle, 2007; Williams & Steinberg, 2011; Zimmerman &

36
Arunkumar, 1994). Studies have also noted that a lacking upbringing links to attention
regulation deficits, poor language skills, lack of self-control, hyperactive disorder, poor
information process, and aggression. In sum, poor home upbringing and violence
exposure can deter adolescents’ resilience and their abilities to organize, recall, and
encode information process and the ability of expression (Fodor, 2010; Lazarus, 2000;
Miller et al., 1999). Additionally, exposure to violence can lead to emotional effects.
Emotional Effects
Emotional effects of domestic violence are characterized as a negative exposure
that almost always carries consequences, particularly when such experiences become
frequent in the home (Job, Bernecker, & Dweck, 2012; Kliewer & Murrelle, 2007).
Overstreet and Braun (2000) confirmed that intrafamilial violence often leads to anger,
agitation, withdrawal, isolation, depression, poor problem solving, self-harming and
negative self-concepts. Researchers reported that witnessing and proximity to violence, as
well as being a victim, could increase anxiety and depressive symptoms that would
change adolescents’ worldview about their social environment (Grigorenko & Sternberg,
2003; Johnson et al., 2002; Löckenhoff, Reed, & Maresca, 2012). Thus, whether this
violence is related to immediate family or to community types of violence, adolescents’
resilience development can be compromised. This effect results in other psychological
consequences, such as PTSD, poor concentration, sleep disorder, sudden startling, anger,
tantrum, delinquency, poor task accomplishment, low self-esteem, uninspired, and
intrusive raising thoughts (Alvord & Grados, 2005; Flowers, Hastings, & Kelley, 2000;
Guillaumin, 2002; Pang, 2010a).

37
Young adults with emotional disorders have often been stigmatized (Boydell &
Ferguson, 2012; Grotberg, 1999) because of their involvement in high risk behaviors and
poor lifestyle. These behaviors, however, should lead researchers and clinicians to
question not the person, but the person’s development process (Alvord & Grados, 2005).
The answer to this question may lie within the unresolved family issues to which
responses are exhibited (Carlson, 2000; Zautra, Hall, & Murray, 2010). Moreover, these
emotional influences can lead to behavioral and social consequences.
Behavioral and Social Effects
It is evident that early childhood development and exposure to violence can
initiate social and behavioral deficits (Zautra et al., 2010). For example, when parental
tactics to teach a child, family values, self-control, and responsibility become ineffective,
it could result in self-defense mechanisms (Calrson, 2000). Negative self-defense
mechanisms not only interfere with the child’s efforts to attain personal goals, but also
hinder information processing to regulate emotions and to understanding of human life,
values, properties, and the society’s expectations (Feldman, 2003; Lock, 2000). The
emotional deficits, irritation and anger characteristic of the adolescent stage can
progressively develop into false identity and low resilience (Kaufman et al., 2000; Linley,
2003).
One study that confirmed the behavioral influence of domestic violence was
conducted in a large number of (140) adolescent participants comprised of experimental
and control groups to which a number of psychological tools were administered,
including the Millon Clinical Multiaxial Inventory (MCMI; Dutton, 1994; Dutton &

38
Starzomski, 1994), the Minnesota Multiphasic Personality Inventory (MMPI; Dutton, van
Ginkle, & Starzomski,1995), Borderline Personality Organization (Straus & Gelles,
1990), and the Conflict Tactics Scale (Saunders, 1996) to identify triggering factors for
poor behaviors. From a treatment perspective, the experimental outcome revealed that
adolescent borderline personality organization was found in 11 to 15 percent of the
participants due to home violence (Dutton & Golant, 1995; Nastasi & Bernstein, 1994).
In summary, studies on adolescents’ emotional behaviors have long-term
traumatic consequences triggered by poor environment and intra-familial violence for
poor impulse control (Feldman 2003; Johnson et al., 2002; Lippold, Greenberg, &
Collins, 2013). These influences have long term effects for individuals exposed to
domestic violence in their homes, and may alter the way that individuals behave,
according to Bronfenbrenner’s theory. The confluence of these effects are often felt when
a child who has been exposed to domestic violence is placed within a foster home or
treatment facility. Moreover, these effects will continue to influence the individuals’
behaviors as a young adult (Lipton et al., 2013).
Because abuse reports have been exposed in many states’ residential treatment
centers (Cancio & Johnson, 2007; Kernberg et al., 2012; Phillips, Leathers, & Erkanli,
2009), JCAHO has established minimal requirements and expectations for Residential
Treatment Centers (RTC; Cancio & Johnson, 2007; McGuffin, 1991). In 1999, following
policies developed in the 1960s, 1970s, and 1992 for foster home and treatment facilities
to meet adolescents’ psychological and emotional needs, the U.S. Surgeon General, in
collaboration with JCAHO, required each RTC to provide admission policy that will

39
grant positive impact for resilience formation (Black et al., 2015; Chen & Ma, 2007) The
Surgeon General and the JCAHO set limitations on admission policies that disallow
unqualified residential treatments centers for operation. This decision was based on
Werner’s 1982 research on adolescents’ resilience on the Hawaiian island of Kauai,
which continues to set the standard for many professional organizations today. The
following examines Werner’s adolescent resilience overview adopted by the Surgeon
General and the JCAHO.
Prior to the 1980 act, dependent minors lived in many different foster homes and
in different neighborhoods because of aggression and acting out behaviors because of
exposure to domestic violence which led to poor academic achievements (Black et al.,
2015; Pelton, 2008). In 1993, Californian foster parents reported that most children
attended an average of 9 different schools by age 18 and demonstrated significant poor
academic achievement, truancy, poor self-esteem, anger, and shame (Kaufman et al.,
2000; Kernberg et al., 2012). The children’s educational discontinuity as reviewed by
Kaufman suggests that there are multiple negative emotional consequences to a child’s
removal from one home/facility to another. Kaufman also expressed that inadequate
adolescents’ academic record transfer and loss of credits may contribute to poor school
performance and lack of resilience for success.
For these reasons, 70% of minors in foster homes/facilities have significant
domestic violence, abuse histories and other behaviors that led to mental health problems
promulgated by the observed domestic violence and poor home environment (Finlay,
Darlington & Nicastro, 2001; Mowder et al., 2010). Cancio and Johnson (2007) noted

40
that appropriate psychological academic evaluation as proscribed by the individuals with
disabilities act (IDEA) can improve the individual’s academic success, rather than
leaving the child to dwell in the vicarious impacts of domestic violence. While we
continue to see the lack of this accommodation in some chartered schools in the Southern
region of the United States, only 15% graduate from high school, which is below the
American taxpayers’ expectations (Cancio & Johnson, 2007; Kleinman et al., 2013).
In recent years, domestic violence has been reported as a major contributor to the
over 6% annual increase in child dependency in the United States (Lloyd & Emery, 1994;
Mowder et al., 2010). According to Greene, Coles, and Johnson (1994), the 1985 and
1996 reports suggested that over 2.9 million adolescents’ dependency increased. In 2005,
a report was submitted to the house committee who were assigned to investigate the truth
of this claim. It was found that both foster homes and treatment facilities population have
decreased 37% between 1994 and 2000 in both academics and admissions (Chambers,
2008; Kumar et al., 2010). Based on analysis of the timeline of these reported estimates,
American society is not necessarily declining in child dependency cases and treatment
facility and foster homes are not necessarily declining.
According to Yehuda’s (2004) report, it was observed that there are many
treatment facilities and foster home care services being built in Bexar County (Texas),
California/Los Angeles, Orange County, Colorado, Michigan State, and New York. The
U.S. Advisory Board on Child Abuse and Neglect (USABCAN, 2010) argued that the
decline in minor placement or the decreasing number of foster homes and treatment
facilities is misleading, leading society to pay minimal attention to the cause of

41
adolescents’ removal from home, emotional stress, and psychological needs as a result of
domestic abuse. Moreover, this decrease may influence the policymakers’ views of the
importance of this social phenomenon (Howell, 2008; Lanza & Taylor, 2010).
In summary, as of 2008, research shows that about 650 nongovernmental
residential programs have been built nationwide with certain program methodologies to
deliver treatment plans that would address adolescents’ psychological and emotions
needs in their quest for resilience (Karol et al., 2015; Martin & Pear, 2007). These
statistics indicate that, in terms of decline in adolescents’ dependency and placement,
nothing has changed (Monique, 2015; Phillips et al., 2009). To gain a more accurate
measurement, the field must reconsider the approach from which these studies were
conducted, examines the methods, and verify whether researchers focused mainly on
government facilities rather than including non-profit or privately owned operated
facilities and the policies that affect private and non-profit program agencies.
Policy Impacts on Facility Programs and Methodologies
After the policy review in the 1980s, foster homes/facilities, quality program
methodologies have varied greatly given the federal status of limitation for adolescents’
behavioral modification intervention reinforcements (Cancio & Johnson, 2007; Martin &
Pear, 2007; Monique, 2015). For example, the southern region of the United States is one
of the regions in the United States that house 133 out risk adolescents, male and female
residents that other private and foster homes would not accept because of the limitation of
operation and licensures. The Southern region of the U.S. facility is licensed to use
approved protocol to administer psycho-emotional treatment to individuals exposed to

42
domestic violence and abuse. Thus, the behavioral modification process is based on the
regulatory act that compels the facility to use certain methodologies to affect therapy
procedures. These methodologies include the use of point accumulation by each resident
at the end of each clinical hour activity to reward good behaviors, while restrictions
including point deductions, status reversal, treatment extension, and physical restraint are
employed by the facility policy to confront and modify behaviors (Henrichs et al., 2015;
McGuffin, 1991; Phillips et al., 2009).
These methods may not be used in other facilities because of individual facility
state regulations. However, critics have considered this method of operation unequivocal
to behavior modification as it does not implement criteria for resilience. Again, instances
of abuse have been reported in most residential treatment facilities and foster homes,
which prompted the JCAHO to investigate these reported incidences (Kernberg et al.,
2012; Underwood et al., 2008). In most cases, JCAHO finds that the use of consequences
as therapeutic models for behavior modification is successful as long as the methods are
supervised by licensed therapists, medical personnel, and quality complaint
administrators to prevent flashbacks to the individual’s past abuse violent experiences
(Cancio & Johnson, 2007; Chen & Ma, 2007; Monique, 2015). These behavioral
modification programs may facilitate the development of resilience among adolescents
who have been exposed to domestic violence.

43
Resilience Historic Overview
Resilience Defined
Resilience is an individual’s ability to bounce back regardless of the individual’s
environmental circumstances (Daining, 2005; Hopf, 2010; Jaffe, 1998). Resilience also
refers to the ability to seek or acquire personal and cultural resources that create a
meaningful interaction with others. Most academics agree that resilience refers to an
individual’s skill at continuing normal developments despite environmental adversities
(Deal, 2000, 2002; Siemieniuk, Krentz, Gish, Jessica, & Gill, 2010). Many researchers
concluded that exposure to trauma can create an instinct to certain responses for survival
(Dietz et al., 2014; Ungar et al., 2008). In much of the literature, it has been demonstrated
that resilience emerges when individual efforts are threatened (Gish, Jessica, & Gill,
2010; Masten, Best, & Garmezy, 1990).
The Emergence of Resilience in Treatment Facilities
Prior to resilience research, some studies devoted extensive work to adolescents’
behaviors as opposed to focusing on protective factors to explain catastrophic life event
responses to stages of adulthood transitions. These researchers failed to explain how the
individual’s traits and temperament led to poor resilience (Cicchetti & Rogosch, 1997;
Fredrickson, Tugade, Waugh, & Larkin, 2003; Garmezy & Streitman, 1974). From
Rutter’s, Bronfrenbrenner’s and Werner’s findings, the term “resilience” has developed
into a major theoretical research framework of topics that investigates the environment in
terms of its adverse effects on human adversaries (Werner & Smith, 2001; Yoon et al.
2015). Arguments have surfaced, however, disputing Rutter’s, Bronfrenbrenner’s, and

44
Werner’s findings that children living with schizophrenic parents show low resilience
compared to adolescents living with healthy parents because of the parents’ poor abilities
to ,care for these adolescents’ basic needs (Luthar, 1999; Thrash, Cassidy, Maruskin, &
Elliot, 2010). Despite this controversy, some adolescents have reported adjustment to
adversity and success in setting personal goals for future achievements (Davies, Winter,
& Cicchetti, 2006).
In sum, Werner and Rutter’s network of research has provided awareness about
adolescents’ behaviors. This awareness educates practitioners about the individual’s drive
toward self-fulfilling (Benard, 1991; Damant et al. 2010; Werner & Smith, 1992). The
studies also pay greater attention to cultural and an individual value, which indicates that
resilience, can be understood as a social construct associated with an individual’s
worldview or the ability to navigate social norms successfully or compress negative
emotions as the individual begins to become aware of the social environment (Garmezy,
1991; Masten & Powell, 2003; Mowder et al., 2010; Williams & Steinberg, 2011).
Resilience among Young Adults
Scholars have credited Garmezy (1973) and Ungar et al. (2008) as first to study
adolescents’ resilience, although their study methods were based on epidemiology that
focused on reasons some adolescents’ are more resilient than others, which also relate to
how much resilient those individuals may carry along to adulthood functioning. Garmezy
proposed that some protective factors, such as rewards, praise, recognition, goal setting,
and self-esteem, are criteria for resilience development. Conversely, poor environment

45
and low self-esteem could lead to self-indulgence and poor behavior imitations (Black et
al., 2015; Henrichs et al., 2015; Nastasi & Bernstein, 1998).
Unlike Garmezy, Werner, an American developmental psychologist, investigated
the impact of social environment on adolescents’ resilience and their ability to maintain
such traits in adulthood life. In Hawaii where this research was conducted, Werner found
that, depending on the individual’s temperament; at-risk adolescents can make good
choices (Werner, 2004) that adolescents may be bound to fail in their quest to achieve
adulthood functioning requirements in the society. This finding was based on the
longitudinal study of 698 participants in the Hawaiian island of Kauai, where
reproductive factors for resilience included not only domestic violence, but also
premature birth, unstable household, parental substance abuse, exposure to intimate
partner violence (IPV), and mental health (Black et al., 2015; Masten & Powell, 2003;
Yoon et al. 2015). In continuation, Werner revealed that some adolescents exposed to
high environment risks may have no delinquent behaviors or mental/physical health
problems compared to those exposed to fewer risk factors as transition to adulthood
continues to occur (Prince-Embury & Steer, 2010; Werner, 1982). Werner and her
colleagues identified a number of protective factors that helped the studied population
thrive, which include strong bonding relationships, aunts, babysitters, teachers, religion,
adult role models, and community group organizations for the individual’s development
in the absence of biological parents (Prince-Embury & Steer, 2010; Werner, 1982).
Similarly, Masten and Powell (2003) found that one third of all high-risk adolescents
exhibited resilience and developed into caring, competent and confident young adults,

46
despite poor developmental experiences. Additionally, Rutter (1980) found that although
high-risk adolescents were more likely to develop behavioral issues that tend to militate
against their transitioning preparation to adulthood than were the general population;
however the majority of those adolescents have shown resiliency and have developed into
competent, healthy productive adults. Rutter also found that even though most
adolescents were living in disadvantaged homes, they spent more time with positive peers
and were able to develop strong personalities, positive thinking, and goal setting
behaviors that motivate problem solving skills and efficacy towards self-actualization.
Coburn and Nelson (1989), Geary (1988), and Werner and Smith (1987)
confirmed that the presence of role modeling adults, good health, teachers, goal-setting
and aspiration to excel in life can play important roles in adolescents’ protective factors
for adulthood transitioning. Thus, the outcomes suggested that good physical health,
positive thinking and communication with role model adults can foster adolescents’
abilities to handle different life challenges and make commitments for a long term goal
and success. These findings complemented Werner’s observation that adult role modeling
can foster neurological development that increases the immune system against diseases
and better choice-making processes for smooth transitions (Mowder et al., 2010; Sorbello
et al., 2012). Additionally, heredity and family bonding imprint meaningful interaction
towards building quality and healthy relationships consistent for resilience development
from childhood to adolescence; therefore paving ways upon which adulthood transition
could be made possible without counter-interact with other associated negative militating

47
community factors (Bonem et al. 2008; Burgos-Cienfuegos, 2015; Rutter 1980, 1984,
1985; Williams & Steinberg, 2011).
In sum, resilience formation is closely associated with adolescents’ self-
awareness, self-appraisal, and the perception of the social environment for the
development of emotional stability towards successful young adults. Adolescents’
protective factors have become the focus of many studies because of the exploration of
asset-based evidence that reinforces resilient intervention plan in the quest to empower
adolescents for successful adulthood transitions (Damant et al., 2010; DeForge et al.,
2005; D’Imperio et al., 2000; Resnick et al., 1997; Rutter, 1985). Interventions in
treatment facilities and previously developed resilience among these adolescents that are
preparing to transition to adulthood may potentially help to mitigate the harmful effects
that upbringing may cause in achieving this tendency. The following section discusses
the development of resilience in treatment facility environments.
Resilience in Treatment Facility Environments
The literature indicated that the accumulation of adolescent’ daily risk factors can
lead to mental health problems (Burgos-Cienfuegos, 2015). Similarly, studies have
emphasized that adolescents’ risk factors are related to the increase rates of self-harming
tendencies, anger and frustrations, fighting, alcohol and drug abuse, juvenile delinquency
issues, suicide, depression, and spending time in the juvenile detention/treatment
facilities (Beam, Gil-Rivas, Greenberger, & Chen, 2012; Plancherel & Bolognini, 2012;
Storksen, Roysamb, Moum, & Tambs, 2010). Alternatively, these risk factors among
adolescents may lead to the development of resilience as young adults (Karol et al.,

48
2015). Interventions in treatment facilities may assist in the development of these positive
behaviors.
Dutton and Starzomski (1994) conducted a study that involved 78 self-referred
and court-referred male and female adolescents undergoing treatment for aggression, low
self-esteem, and depression in a treatment facility setting. The results showed that over
65% of the entire sampled population had clinically significant self-blame from domestic
violence, while 35% reported borderline personality disorder due to poor environment
upbringing. These findings confirmed the studies of Hamberger (1994) and Starzomski
and Nussbaum (2000), which stated that borderline personality disorder is found in
adolescents who lacked parental bonding and adult role models. Additionally, the poor
lifestyle developed by adolescents in a poor home environment can accumulate to low
self-esteem (Goodrum et al., 2012; Kesner, Julian & McKenry, 1997). Thus, the
individuals who enter treatment facilities frequently suffer from behavioral issues due to
their previous circumstances.
However, researchers have demonstrated that adolescents who spend more time
with adults can develop self-control, good feelings, and self-expression, leading to an
improved worldview (Fantuzzo et al 1997), Lepore & Greenberg 2002). Studies have also
shown that expressive writing increases adolescent’ verbal skills to express what
happened to them in their individual homes, improve self-esteem, social network, values,
goal achievements, characteristics, and respect (Garthe et al., 2014; Lepore & Greenberg,
2002). Hamberger and Hastings (1991) examined these characteristics among adolescents
admitted in a treatment facility and confirmed that adolescents that spend more time with

49
adults are motivated to stay on tasks. Hamberger and Hastings revealed that 75% of
adolescents who lacked adult role models develop psychopathology associated with
antisocial behaviors and borderline personality disorders while the other 25%
problematically ignore negativity and have problems opening up in therapy. These
findings were further supported by later researchers (Goodrum et al., 2012; Schwartz et
al., 2014).
Adolescents and Young Adults Exposure to Domestic Violence
The ongoing effect of domestic violence exposure on adolescents is yet to be
understood in the context of what we should know or how significance the impact of
domestic violence may affect a child. A child who has been exposed to domestic violence
often may exhibit changes in behaviors and some changes in the dynamics of maturation,
especially around the puberty period (Schwartz et al., 2014), that may carry on following
the transition to adulthood. Since adolescents’ mental health or health in general may
disrupt the developmental process, failure to recognize the challenge could lead to
resilience decline, therefore causing some emotional deficits limiting a complete
transition from adolescents to young adulthood. However, concentrating on young adult
mental health and behavior outcomes in a simple paradigm provides a better prediction
and the understanding about adult life trajectories than outcome assessment as observed
in adolescents, which allows adolescents to perceive themselves as more matured than
others. Fergusson, Boden, and Horwood (2008) proposed in their large-scale population-
based prospective studies using diagnostic measures to address the question whether

50
adolescents exposed to domestic violence predicts young adult behavioral response
outcome. Prior to this study, no previous researchers examined this relationship.
Consequences of Domestic Violence Exposure
Amato and Sobolewski (2001); Lieberman, Chu, Van Horn, and Harris (2011);
and Nayak, Lown, Bond, and Greenfield (2012) have suggested that in spite of other
studies in this area, growing up in a home characterized by domestic violence and its
concomitant experiences, such as child-case hearing at the court, custody battle, and
divorce, may also contribute to greater psychological distress with decreased self-
esteem, loss of hope, life-role, and independence, resilience formation, and other
emotional well-being in young adulthood. The outcome was largely reported in cross
sectional designed studies. Other evidence suggested that domestic violence effects on
adolescents can manifest in aggression, stagnant growth, substance abuse, low self-
esteem, runaway, self-harming, demoralize potentials, emotional withdrawal, attention
problems, poor school achievements, poor decision making, procrastination tendencies,
low resilience, and psychiatric symptoms (Beam et al., 2012; Plancherel & Bolognini,
2012). Consequently, these negative transparencies may be carried into adulthood and
affect the young adults’ broader external stimuli responses (Lieberman, Chu, Van Horn,
& Harris, 2011).
Cisler et al.’s (2012) longitudinal study of the effects of domestic violence on
adolescents was found to be one of the many reasons they are admitted to treatment
facilities as transition to adulthood could become a lifetime struggle. In 2012,
longitudinal studies were conducted on adolescents who made a successful transition to

51
adulthood. A national survey among adolescents ages 12–17 (N = 3,614 at Wave 1) to
investigate whether exposure to domestic violence at Wave 1 was associated with PTSD,
depression, excessive alcohol use, and delinquency (Cisler et al., 2012). The longitudinal
study also examined Wave 2 and 3 a year later respectively. The finding was that
exposure to domestic violence at Wave 1 associated with adolescents’ depression,
delinquent acts and binge drinking at Wave 3 (Cisler et al., 2012). The same research
group also conducted another study using the another data set in their investigation and
found that there is associations between adolescents’ who have experienced traumatic
events such as: verbal abuse, physical abuse, emotional abuse, sexual assault, witnessing
parental conflicts or community violence at Wave 1; while substance behaviors was
consistent among the participants group at Wave 2 after 15 months of the study. By
aggregating all types of victimization adolescents may have been through all together to
report their findings, it appears that adolescents’ victims have difficulties transitioning to
adult life after exposure to domestic violence. Consequently, the findings generally stated
that after examined the entire studies conducted in this area; there are few research that
have used a longitudinal design to investigate the outcome of domestic violence on
adolescents.
None of the reported studies utilize the longitudinal design to examine fully the
factors that influence resilience development after domestic violence exposure.
Therefore, it is necessary to gain more data regarding the experiences of the young adults
after exposure to gain an idea of the factors that influence their resilience development. In
addition, while these studies examined the effect of domestic violence on adolescents by

52
utilizing self-report or mother report scales oftentimes found in Child Behavior Check-
list (CBCL) as evidenced in Howell (2011) and Lamers-Winkelman, Willemen, and
Visser (2012), this design limited the core value of information what we should know
apropos to this present study which sought to utilize structured clinical surveys to assess
the variables that may influence resilience development.
Exploring Gender Differences and the Exposure of Domestic Violence
The impact of domestic violence may differ by gender. It is worthy to note that
many studies have controlled the significance of gender to report their findings.
Consequently, very few studies have examined gender differences directly and have
reported different outcome that appeared different from other studies. Even when some
studies that included gender differences failed to report their findings on what was
measured (gender differences) or the significance thereof (Kitzmann et al., 2003; Lamers-
Winkelman et al., 2012; Wolfe, Crooks, Lee, McIntyre-Smith, & Jaffe, 2003). All these
gaps create misconceptions leading to underreporting what we should know about the
impact of domestic violence exposed children, adolescent as the population makes their
transition to young adults’ life. Two recent studies examined gender differences in the
context of adolescent exposure to domestic violence. Skeer et al.’s (2011) study was
based on longitudinal data from the Project on Human Development in Chicago
Neighborhoods (PHDCN) that included 1,421 young adults aged 18–22 (in Wave 3 of
this study) and adolescents who were 10–17 years when domestic violence in the family
was assessed (Wave 1) using substance abuse and dependence as the main dependent
variable. According to Skeer et al., males living in families where domestic violence is

53
frequent was found not significant to become at-risk for either substance use or other
symptoms, such as anxiety, aggression, or depression. In the same study, it was reported
that unlike their male counterpart females, living in domestic violent homes was
associated with conduct disorder, explosive anger, verbal aggression, fighting, substance
use and emotional dependence (Skeer et al., 2011). On the other hand, Begle et al. (2011)
conducted a U.S. national study following this study with a representative sample of
3,614 adolescents aged 12–17 years of age and 3,536 young adults to investigate the
significance of gender differences outcomes following witnessing domestic violence in
the home. It was found that males are more likely to be affected than females (Begle et
al., 2011), and as a result males are more likely to be admitted to treatment facilities than
their female gender. The differences of opinion in these studies depict that there is a need
to explore gender differences in young adults’ outcomes of domestic violence as children
and this present study is designed to provide detailed scientific findings to add to the
body of knowledge about the influence of domestic violence exposure and demographic
variables on resilience.
Environmental Factors’ Influence on Adolescents’ Resilience Development
The following section identifies environmental and demographic influences that
may promote resilience in adolescents and young adults. For example, male and female
African American adolescents’ values may be different from Hispanics’ and Caucasians’
in terms of a treatment plan based on age, environment, and cultural norms considering
also the environmental issues that may present. Lloyd and Emery (1994) and Dutton and
Starzomski (1993) proposed that adolescents’ culture and gender are pivotal to

54
understanding resilience development, especially as they make another transitional step
toward adulthood, thus, connecting the individual’s age, gender, and culture when
making treatment plans may be essential for understanding and predicting adolescents’
emotional responses to make some self-appraisal in preparation to adulthood functioning.
Starzomski (1993) noted that an adequate treatment plan based on age, gender, and
cultural identity can inspire motivation toward change in lifestyle that influences
resilience. As evidenced in Abbot and Hall (2006); Allen and Allen (2006); Brown
(1997); Rohr (1990); Straus and Smith (1999); Tolman and Bennett (1990); and Waltz,
Babcock, Jacobson, and Gottman (2006), adolescents’ age, gender, culture, events, life
styles, community connectedness, and family bonding relationships are all supportive
dynamic factors that promote resilience and self-betterment to become stabilized and
rational young adults in the society. The following examines the aforementioned resilient
factors.
Some researchers have found that people that are exposed to a variety of
environmental risk factors have significant mental health issues (Black et al., 2015;
Delfos, 2010). Researchers have also demonstrated that adolescents exposed to these
environmental forces have risk factors, including poor self-thought processes, decreased
interest in education achievements, low self-esteem and empathy (Holland, Benson,
Orloswki, Fredison, & Defenburg, 2015), followed by other environmental risk factors
such as bullying in the playground or during lunch time that results in conflicts with
peers. These underage exposures can become the internal locus of control issues they go
through due to poor intervention process performed or low support trends from either

55
parents’ caregivers or teachers and may carry the same unresolved feelings to adulthood
living (Black et al., 2015; Goodrum et al., 2012). The developed disordered thinking in
childhood and adolescence will continue on to a young adults’ mental and physical well-
being.
Researchers have found that the above mentioned risk factors are significantly
related to poor behavioral response in the adolescents’ attempts to build defensive
mechanisms that often times hidden leading to significant mental health problems (Black
et al., 2015; Karol et al., 2015). Alternatively, these factors can work to promote
resilience. Included below are reviews of literature examining how life event, family,
community, and facility or school factors can influence resilience.
Life Event Factors
Based on Rutter’s (1987, 1990) and other similar studies, it is clear that
unexpected life events can pose psychological and emotional threats to how people
respond to circumstances (Brookmeyer et al., 2006; Carroll, 2006; Edwall, 2012; Irby,
2001; Spaccarelli, Sandler, & Roosa, 1994; Wolfe et al., 2003). Following these numbers
of studies, the National Self-Report Database noted that adolescents’ poor life
experiences impact behaviors compared to those not exposed to those experiences
(Patricia & Nancy, 2000). Other similar studies proposed that an individual’s
environment and experiences can also become factors to either accept poor
environmental dictates or become resilient. Bliststein (2005); McElliskem (2006); Huang,
Tajima, and Whitney (2003); Van Breda (2001); and Children’s Health Fund (2011)
supported that adolescents ages 15-17 are more affected by the environmental dictates

56
than those aged 10-14. According to this study, the 15-17 year old adolescents exhibit
high-risk behaviors with little adjustment compared to 10-14 years old; however,
Bornstein et al. (2010), Carlson (2000), and Elliott (1994) reported that regardless of age,
high-risk choices can be observed in every age generated by the individual’s experiences,
encouraged by negative influence to conform in one’s personal life.
Family Factors
Chapter 1 of this study introduced that family values and dynamics can determine
a child’s propensity towards aggressiveness or resilience. Thus, family dynamism in this
study is understood as those values agreed upon as a limited set of responses and
behavior expected of the whole in events that display characteristics and attitudes of the
entire membership. These values include relationships, emotion management,
communication, discipline and respect to the outer groups (Brookmeyer et al., 2005; De
Los Reyes et al., 2013; Kennedy & Minami, 1993; Myers et al., 1993). The relationship
ordained by family members teaches social responsibilities and expectations that not only
unify members through common beliefs, but also provide evidence of what makes them
different from others. In a family where this relationship is lacking, it demoralizes a child
and produce chaos that projects, individualized responses, isolation, lack of discipline and
social accountability (Carroll, 2006; Garthe et al., 2014; Gerard & Buehler, 1999;
Waldon et al., 2001).
A child growing in this family eventually exhibits poor matriculation in his/her
social environment. This modeling behavior occurs not only within the conventional
nuclear families, but also within extended families that are not interested in promoting

57
adolescent’s mental health (Ungar, 2004). Flores et al. (2014) noted that recent studies
have beginning to investigate the effects of domestic violence, community violence,
divorce, child maltreatment and abuse to predict resilience processes. According to Flores
et al., resilience depends on how individual child is raised and supported given the
protective factors from the immediate family and extended family.
Rodgers and Rose (2002) also found that poor parental skills oftentimes resulted
in adolescents’ negative responses to external issues and poor cognition. Furthermore,
family dynamics are linked to adolescents’ attitude, defense mechanisms (Czarnetzki,
2003; Demo & Acock, 1996; Dishion & McMahon, 1998; Emery & Forehand, 1994),
and certain regressive behaviors like eating and sleeping disorders, somatic complaints,
emotional disorders, poor concentration, generalized anxiety and other psychopathology.
Therefore, family dynamics paint a truer picture of a child’s development than diagnosis
of negative behavioral responses (Callie, 2003; Garthe et al., 2014).
Community Factors
Community relationships are necessary for development of resilience because
negative influences can occur when there is a breakdown in family communication
dynamics; as has been demonstrated, every child or adolescent needs adult support to
develop resilient protective factors (Dondero, 1997; Wolkow & Ferguson, 2001).
Rodgers and Rose (1994) clarified that these relationships are particularly lacking in
families with single working parents. Without the presence of coaching adults or nuclear
family, these minors are prone to negative environmental trauma. Thus, for instance, in a
community where drugs and alcohol are the community culture, adolescents growing up

58
in that community can be quickly influenced to engage in similar behavior (Dietz et al.,
2014; Zimmerson et al., 2002). Conversely, a number of studies found that the presence
of coaching adults through sports involvement, community activities and volunteerism
enhanced self-esteem, intelligence, problem solving, task orientation, achievements,
respect for others, and goal actualization (De Los Reyes et al., 2013; Garthe et al., 2014;
Grossman & Tierney, 1998; O’Donohue & Ferguson, 2006).
However, some have argued that the cause of poor behaviors is a combination of
poor family dynamics and community violence. Olchowski, Foster, and Webster-Stratton
(2007) found that there was no relationship between community factors in adolescents’
manifestation of poor behaviors, depression, anxiety, and stress symptoms. Although
certain emotional symptoms may exist regardless of community’s morals, an individual
may apply immediate family values to make choices and set personal goals (Jacobson &
Mufson, 2010; Underwood et al., 2008). All the same, community mentorship and
support have proved effective in the adolescents’ decision making process. To this end,
Stoiber and Good (1998) agreed that adolescents can derive resilience from community
adult role modeling and mentorship to deter aggression as evidenced in
Bronfrenbrenner’s ecological systems (Thomas, Goodman, & Kundey, 2013).
Facility or School Factors
Another factor that may lead to the facility or school influencing resilience is the
intervention available at a facility. Whether a child is enrolled in the public school or in
an RTC, the environment can become the center for building behavior/emotional
development (Olchowski et al., 2007). Although most RTCs are classified as therapeutic

59
boarding schools or emotional growth boarding schools (Bohensky & Maru, 2011;
Gallant & Lafreniere, 2003), the system implements behavior modifications that provide
structured routines with specialized supervision programs that facilitate therapy and
educational formation to improve self-control (Callie, 2003; Howard & Johnson, 2000b).
The system also provides a safe environment that helps adolescents develop a sense of
purpose, goal achievement, sense of community, responsibility and emotional
connectedness that impact moral values for social skills, college preparatory, problem-
solving, social competence, and self-respect. Although resilience may not occur in the
classroom alone, peer interaction during recreation has proven to increase sharing
individual experiences, encouragement, self- discipline and efficacy for resilience
building (Gableet al., 2004; Thomas et al., 2013). In sum, facility school system provides
adolescents modeling behavior through staff members and positive peer interaction that
encourage personal values and strength for goal attainment.
Grotberg (2010) noted that the most reliable predictors of resilience are not
demographic, but rather the individual’s internal locus of control. In spite of demographic
differences, high-risk individuals that are unable to manifest resiliency may perceived
their social environment as random and uncontrollable (Lanza & Taylor, 2010).
Cultivating the sense of control over the environment among troubled adolescents may
therefore increase resilience (Grotberg, 2010). However, the perception that an
adolescent has over their self-efficacy in this area may be determined by demographic
variables, although this aspect of the literature has not been examined. The following

60
section reviews what literature has been published regarding demographic factors and
their influence on development of resilience.
Demographic Factors’ Influence on Young Adults’ Resilience Development
As yet, many studies on domestic violence experiences have only focused on risk
behaviors and environmental factors regarding the development of resilience, rather than
emphasizing demographic factors (Bondü & Krahé, 2014; Kelly, 2000; Tedeschi &
Kilmer, 2005). Carlson (2004) suggested that in spite of adolescents’ low resilience to
external adversaries, not all adolescents from violent homes exhibit poor behavioral
responses. These differential responses may be tied to demographic factors. Some
demographic factors that researchers have determined may influence the development of
resilience include age, gender, and ethnicity. Age, gender, and ethnicity variables may
provide the asset-base to determine individual’s experiences with resilience formation
(Edleson et al., 2007; Edleson et al., 2008; Osthoff 2002).
Age and Resilience
Age is the duration of an organism or a thing between the beginnings of a being at
any given time aiming at maturation (Bogat, Levendosky & von Eye, 2005). According
to Löckenhoff, Reed, and Maresca (2012) and Olchowski et al. (2007), an individual’s
age is significant in research to determine how each individual may view child
abuse/domestic violence. Studies related to the influence of age on the development of
resilience have been fairly consistent in showing that the later an individual is exposed to
a risk factor, or the earlier an intervention is made, the more likely it is that the individual
will develop resilience (Ali et al., 2015; Garthe et al., 2014; Jan et al., 2015).

61
For example, Ali et al. (2015) determined that children who were exposed to
domestic violence early have lesser chance to acquire resilience compared to those who
were totally removed from the violent environment early on in their lives. On the other
hand, Garthe et al. (2014) determined through logistical regression analysis of 132
children living in a foster care family who had once been exposed to domestic violence
that resilience could be maximized when early interventions were made (Garthe et al.,
2014). Garthe et al. concluded that children that were removed from violent environment
early met criteria for resilience when compared to a population of children who were left
in a violent environment unattended
Another retrospective study conducted by Jan et al. (2015) focused on 122 adult
male and females who were exposed to community violence, family violence and abuse
as children. Jan et al. used logistical regression analysis to analyze the data, and found
that children exposed to aggression in their early age were almost twice as likely to
engage in aggression and poor behaviors and were less likely to evidence resilience. Jan
et al. further determined that because these children had no supportive system, and lived
in a harsh environment without early removal, they developed ego-resiliency and ego-
control and defensive mechanism as the best emotional attachment options to meet their
daily survival needs. However, research on the influence of age on the development of
resilience remains sparse, and requires further validation. Another demographic variable
that may have a relation to the development of resilience is gender.

62
Gender and Resilience
Many studies have reported that gender has significant effects on a child’s coping
skills (Bornstein et al., 2010). For instance, Dadds, Atkinson, Turner, Blums, and
Lendich (1999) used neurological development to propose that adolescent males may
respond differently compare to female counterparts of the same culture. Regarding males’
coping mechanisms, Dietz et al. (2014) reported that adolescent males and females
function differently when it comes to environmental difficulties, including their
temperament and instinct acquired through family or nuclear family cultural values and
tradition dynamics. Specifically, Dietz et al. found that adolescent males tend to make
more use of adaptive coping skills than were females. According to the study, when
males become overwhelmed, their awareness of the problem becomes evident in their
mind and they are ready for a fight (emotionally and physically), thus they tend to cope
by externalizing their ego-control and become focused and directive in their actions
(Dietz et al., 2014). At same time, adolescent males can become distracted at the pressure
of the militating event and can become self-instructors by taking initiatives to calm
themselves down and develop a sense of wholeness and dominance with a strategic
avenue to extricate themselves from the presented problem (Dietz et al., 2014). Jacobson
and Mufson (2010) conducted a similar study with 120 male adolescents to investigate
gender differences in community violence responses. The regression method apropos to
this study found that adolescent males have more aggressive instinct for self defense and
are more likely to fight only when it is beneficial to their masculine ego-dominance
(Jacobson & Mufson, 2010).

63
Adolescent females have different ways to cope with their environmental
militating forces, including seeking immediate help for support and using community
social resources as sustaining system to achieve redemption (Black et al., 2015). While
adolescent male chose to use physical recreational activities and aggressive reactions
such as sport and fighting to cope with environmental adversities, adolescent females
tend to seek more support from the community and friends than males (Black et al.,
2015). Although these differences in coping mechanisms have been demonstrated, review
of the literature revealed no studies that examined the influence of gender on the
development of resilience. Thus, gender was included as a variable in the proposed study.
Ethnicity and Resilience
The most commonly studied demographic variable that may influence resilience
is ethnicity. Although Kegler et al. (2011) reported that in spite of cultural norms no
single culture is superior to other culture; studies have confirmed that African American
and Hispanic youths have improved strategies for developing resilience than do
Caucasian youth (Holland & Gill, 2010; McKnown-Johnson, & Rhodes 2013; Zautra et
al., 2010). For instance, African-American adolescents are reported to have a driven
instinct for resilience through enhancing interpersonal skills and self-confidence toward
goal attainment with the presence of community member adult role models in connection
with community norm (Zautra et al., 2010).
Alternatively, cultural and ethnic factors may exacerbate or influence the role of
gender in resilience development, depending on the agency assigned to women among
the specific group with which the adolescent identifies (Compton, 2010).

64
Grotberg (2010) examined the role of ethnicity in adolescent resilience in other
countries, using the International Resilience Research Project to investigate what made
some adolescents resilient despite harsh ethnic expectations. The analyses included 1,200
families from 22 countries in 27 sites with children 12-17 years of age to report their
findings. The study identified that there are some cultural/ethnic differences in
development apropos to adolescent resilience formation. Twenty-two different countries
were investigated, and the results indicated that ethnicity plays a significant role in an
individual’s response to social issues. However, these findings were questioned by some
scholars, who argued that the studies’ insufficient data between ethnic groups and
similarities pose problems for their conclusion (Daining, 2011). Additional studies also
examined the impacts of ethnicity, age, life style, life events, and biological make-up as
factors for resilience formation (Mowder et al., 2010; Zimmerman & Arunkumar, 1994).
Gender Issues and Young Adults’ Resiliency
Prior studies reported that gender issue on resilience has significant effect on
adolescents coping strategies (Daining, 2011; Grotberg, 2010). Coping strategies in this
context can be categorized into two identifiable types such as: maladaptive and adaptive
strategies (Bornstein et al., 2010). Male young adults tend to exercise their masculinity to
address their emotional issues and are more likely to make more use of adaptive coping
strategies that focus on the immediate problem solving than their female counter parts.
On the same note, male strategies are extern
alized and more often exercise a direct action
that includes but not limited to distractive and positive self-instruction momentum to
manipulate their internal locus of control (
Holland & Gill, 2010; McKnown-Johnson &

65
Rhodes 2013; Zautra et al., 2010
).
Recent studies also show that males are easily to rush
into resolving issues than taking the time to think about their actions. On the other hand
they act before they think which in most cases ends up in legal consequences unlike their
female gender. On the same study, the authors reported that there is evidence that proves
that girls cope with daily stressors more than their male counterparts by seeking social
support, meeting coaches with whom they can confined on to express their concerns and
are more likely than males to utilize social resources within their reach to cope with
issues (Frydenberg & Lewis, 1993). The conclusion of the differences between genders
submitted that young adult males unlike their female counterparts are more likely to use
physical recreation such as sports, yelling, punching whole on the wall, high breathing
techniques to cope with adversity (Frydenberg & Lewis, 1993).
In spite being under stress, young adult females have been found to use resilience
factors such as using emotional techniques such as crying, befriending other strong peers to
seek emotional support more often than boys (
Daining, 2011; Grotberg, 2010
). More also,
in another study
surveys were administered to 1,109 male and 1163 young adults females
(N = 2492) in 2004 to assess self-perception of resilience and associated protective
factors. Female young adults are found to be more likely to report self-expression,
empathy, personal issues, help-seeking, and goals oriented for future and aspirations.
However, this study did not report cultural implication that may present in their
conclusion.
The studies mentioned above focused on young adults, however few studies
have examined age and gender differences in resilience in treatment facilities in the United
States.

66
In the current study, the effects of gender, ethnicity, and age on young adults’
resilience were examined and reported. The gender differences in individual young
adults’ characteristics and protective factors deserve further investigation, in view of their
potential implications considering also cultural differences for mental health prevention
and adaptation to problem solving skills (Danquah et al., 2010; Flores et al., 2014;
Mowder et al., 2010).
Resilience and Age Among Young Adults
Age is the duration of an organism between the beginning of a being and a given
time (Bogat, Levendosky, & von Eye, 2005). Social psychologists have considered age a
process of development to which individuals respond differently. For instance, Dadds et
al. (1999) used neurological development to propose that young adult males respond
differently compare female counterparts of the same culture (Alvord & Grados, 2005)
based on age, attitude, maturity and body language. As each gender matures through
biopsychosocial neuroendocrine responses associated with different ages, young adult’s
thought process, behaviors and lifestyle continue to struggle to form and to conform to
cultural norms and society’s expectations, that could become struggles for transitional
process to adulthood (Rutter, Pickles, Murray, & Eaves, 2001). Females tend to show
significant maturity than males; however, upon victimization, females may begin to
regress in thought process in spite of age (Danquah et al., 2010; Flores et al., 2014).
In male young adults on the other hand, in spite of age male may use aggression
to display show defiant attitude. Male young adults always and often respond to life

67
struggles and threats with caution but at the same time try to communicate that they are
matured enough to take care of themselves while they still lack sense of self-identity.
Often time both male and female young adults may utilize their age as methods to push
people away and therefore refusing help from a role model coach. This response
however, is indication of their life experiences that allowed them to grow over time
suggesting they know it all (Carlson, 2003; Kelly, 2000; Vitopoulos, Peterson-Badali &
Skilling, 2012). In sum, age significantly influences behavior and can be used to address
resiliency formation in therapeutic setting. As yet, though, many studies on young adults’
domestic violence experiences have only focused on risk behaviors, rather than
emphasizing age demographics considering also cultural implication (Kelly, 2000;
Tedeschi & Kilmer, 2005).
The influence of culture on resilience in general. One element that may explain
the influence that ethnicity could have on resilience is cultural differences in raising
children (Danquah et al., 2010; Flores et al., 2014). Although little has been said about
cultural implications on young adults’ resilience, Kliewer and Murrelle (2007) and
Starzomski and Nussbaum (2000) noted that regardless of ethnic differences,
adolescents’ risk reduction can be fostered by utilizing community norms common to
adolescents for risk minimization (Masten, 2009). Resilience and cultural differences
have been advocated within the field of social work, counseling, and psychology to
understand the individual client’s internal locus of control (Jaffe, 1998). Similarly,
Danquah et al. (2010) used predictive regression analysis and determined that several
factors influenced the development of resilience at different ages, including family

68
dynamics, development functions, number of people in the family, personal resources,
and relationship to each family member as predicting factor for resiliency in the child.
Damant et al. (2010), Daining (2011), and Grotberg (2010) confirmed that
different cultures have different ways of responding to adversity. For instance, Daining et
al. (2011) insisted that Hispanic adolescents have a higher sense of self-control in
adversity compare to other cultures. This trait suggests that Hispanic adolescents who in
contact with their community norms have higher self-worth and resilience. Furthermore,
Kliewer and Murrelle (2007) found that African American and Hispanic teens living in a
supportive community developed a strong bound and sense of cultural pride to associate
within the community. Ungar, Shorey, Cornelius, and Bell (2008) reviewed a number of
studies examining the influence of race, cultural values and individual tradition in
predicting resiliency among African Americans, Hispanic and Caucasians. Ungar et al.
concluded that racial identity buffered against the influence of stress and led African
American, Hispanic and Caucasians youth to competently address adversity within their
environments.
Phinney (1996) indicated that limitations in most studies, especially those that
may not have appropriate knowledge of the society and culture, adversely affected the
definition of the cultural differences between socio-cultural groups. Thus, generalizing
different cultural variables into one component (a unit of analysis) is misleading
compared to specific discussions about whether a particular cultural/ethnic group
perceives itself as an individualistic community or as a collective community. Phinney
(1996) argued that adequate ethnic knowledge between cultural groups may provide a

69
detailed determination whether one culture is more independent— that is, culturally
separated from family affiliations or more prone to self-acquisition than generosity, or
perceives self-fulfillment as more important than interpersonal harmony (Daining, 2011;
Grotberg, 2010). In most countries where researchers disregard the differences between
ethnic groups, assumptions about universality can become a problem as a unit of analysis
rather than the differences along which individuals and groups and how they vary from
each other (Grotberg, 1995; Phinney, 1996). Thus, the present study attempted to avoid
universalizing assumptions about culture, despite using ethnicity as a demographic
variable in the potential model.
Domestic Violence and Resilience
Previous researchers primarily suggested that domestic violence has negative
cognitive, emotional, and behavioral and social effects for individuals (Job et al., 2012;
Löckenhoff et al., 2012; Sorbello et al., 2012; Williams & Steinberg, 2011). Regarding
resilience, researchers have turned their focus to asset-based evidence, which suggests
that prior experiences may have provided young adults with protective factors that
allowed them to maintain resilience despite adversity (Damant et al., 2010; DeForge et
al., 2005; D’Imperio et al., 2000; Resnick et al., 1997; Rutter, 1985). However, review of
the research revealed no discussion of a predictive model of resilience among young
adults. The experiences with domestic violence may have influenced the resilience
development of young adults (Anderson et al., 2012; Kassis et al., 2013), and
demographic factors may similarly influence the results.

70
Some research suggested that domestic violence might promote resilience, acting
as a protective factor against further negative influences. Anderson et al. (2012)
conducted a mixed methods study of 37 women who had previously been in a domestic
violence relationship. Anderson et al. assessed whether psychological, sexual, and
physical abuse influenced posttraumatic stress disorder and resilience. Results of Pearson
correlations suggested that earlier exposure to abuse correlated with increased
posttraumatic stress symptoms, and higher education levels correlated with decreased
posttraumatic stress. On a range of 0—100, participants in the sample had a high average
resilience score (74.97), and higher scores in resilience correlated with lesser
posttraumatic stress symptoms. Thus, Anderson et al.’s results suggested that a strengths-
based view of domestic violence victims might emphasize resilience as a correlation with
domestic violence exposure.
Alternatively, exposure to domestic violence might reduce resilience. Among a
sample of middle-school students from Austria, Germany, Slovenia, and Spain (N =
5,149), Kassis et al. (2013) determined through multiple linear regression that negative
experiences, such as domestic violence, poor parenting, and alcohol and drug abuse,
reduced resilience to domestic violence. Related to the present study, Kassis et al. found
that structural variables, including gender and socioeconomic status, did not influence
resilience development. However, Kassis et al.’s findings contradicted a significant body
of literature regarding demographics’ influence on resilience, including age (Ali et al.,
2015; Garthe et al., 2014; Jan et al., 2015); gender (Black et al., 2015; Dietz et al., 2014);
and ethnicity (Danquah et al., 2010; Flores et al., 2014; Holland & Gill, 2010;

71
McKnown-Johnson & Rhodes, 2013; Zautra et al., 2010). In fact, in a follow up analysis
on the same data, Kassis et al. (2015) determined that reliable gender differences existed
in protective and risk factors between the genders. Additionally, Kassis et al. determined
that modifying the home environment could influence resilience status within the sample.
Together, the findings of these studies suggested that additional research should be
conducted on demographics, domestic violence, and resilience.
Summary
In summary, studies have found that a variety of factors contribute to
development of low or high resilience (Callie, 2003; Gableet al., 2004; Garmezy, 1994).
Understanding resilience within adolescent mental health treatment facilities is important,
as risk factors among adolescents increase rates of self-harming tendencies, anger and
frustrations, fighting, alcohol and drug abuse, juvenile delinquency issues, suicide,
depression, and spending time in juvenile detention/treatment facilities (Beam et al.,
2012; Plancherel & Bolognini, 2012; Storksen et al., 2010). Identifying factors that could
predict resilience within this population could help practitioners to develop targeted
treatments for addressing the influence of protective factors, or addressing factors which
negatively predicted resilience. As yet, the research was limited with regards to predictive
models for resilience among young adults. The lacking investigation of the predictive
value of demographic variables and domestic violence on resilience constituted a
significant gap in the literature.
Demographic factors that might influence resilience development included age
(Ali et al., 2015; Garthe et al., 2014; Jan et al., 2015); gender (Black et al., 2015; Dietz et

72
al., 2014); and ethnicity (Danquah et al., 2010; Flores et al., 2014; Holland & Gill, 2010;
McKnown-Johnson et al., 2013; Zautra et al., 2010). Extensive research revealed one
study that contradicted the suggested influence of demographic influences on resilience
(Kassis et al., 2013), but the researchers had focused on adolescents who remained in the
domestic violence situation, and explored only gender, socioeconomic status, and
migration status. Still, the research was lacking in developing the predictive value of
these demographic variables in resilience development, particularly with regards to age
and gender. These predictive factors are worthy of consideration in future study to
explore resilience. Additionally, factors within the mesosystem related to domestic
violence, such as exposure to domestic violence, individual emotional and physical
abilities, types of domestic violence exposure, and frequency of domestic violence
exposure might also influence resilience development.
The research regarding the influence of domestic violence on resilience was
conflicted. In a sample of women exposed to domestic violence, Anderson et al. (2012)
demonstrated that resilience within domestic violence survivors was high. Conversely,
Kassis et al. (2013) determined that negative family experiences, including domestic
violence, negatively predicted resilience within a population of adolescents who
remained in the domestic violence situation. In the proposed study, a sample of young
adults was studied. These young adults were pulled from the BBBS organization. Given
the contested nature of resilience among domestic violence victims, it is essential to
further understand the predictive value of domestic violence for resilience within this
particular population.

73
Based on the gaps in the literature, it was unclear whether age, gender, ethnicity,
exposure to domestic violence, individual emotional and physical abilities, types of
domestic violence exposure, and frequency of domestic violence exposure predicted
resilience among young adults. The purpose of this quantitative study was to examine
whether domestic violence, age, gender, ethnicity, individual emotional and physical
abilities, types of domestic violence exposure, and frequency of domestic violence
exposure can adequately predict resilience among young adults in the Midsouth region of
the United States. In Chapter 3 of this study, I will explore the methodology used to
pursue this purpose.

74
Chapter 3: Research Method
Introduction
The purpose of this quantitative study was to explore whether the predictor
variables of domestic violence, age, gender, ethnicity, individual emotional abilities,
individual physical abilities, types of domestic violence exposure, and frequency of
domestic violence exposure can adequately predict resilience among young adults in the
Midsouth region of the United States. I measured the predictor variable, domestic
violence, using the CEDV scale; I measured the criterion variable, resilience, with the
Resilience Scale. I investigated the following research question: Do domestic violence,
age, gender, ethnicity, individual emotional and physical abilities, types of domestic
violence exposure, and frequency of domestic violence exposure, when in linear
combination, significantly predicts resilience as measured by the Resilience Scale among
young adults in the Midsouth region of the United States?
In this chapter, I address three main topics, which include (a) the research design
and rationale, (b) the methodology, (c) and the threats to validity. In the research design
and rationale section, I identify the variables, identify how the design is connected to the
research question, explain the time and resource constraints, and show how the design
aligns with existing knowledge in the discipline. The methodology section includes the
population (including the sample size), recruitment procedures, participation, data
collection, and the instrumentation and operationalization of constructs. In the validity
section, I address the applicable internal, external, and statistical conclusion threats in the

75
study. I also address the ethical concerns. Finally, this chapter concludes with a concise
summary, which is a reiteration of the major components of this chapter.
Research Design and Rationale
I grouded this study in a postpositivist worldview; I employed a quantitative
approach to address the research question. This study qualified for the postpositivist
approach because I tested an extant theory by examining the relationships between
variables (Creswell, 2009; Pang, 2010a, 2010b). I used psychometrically sound
instruments that yielded numbered data suitable for statistical analysis to measure the
variables and constructs in this study. I determined the aforementioned criteria fit a
quantitative paradigm as defined by Creswell (2009). Furthermore, quantitative inquiry is
nomothetic becuase quantitative researchers apply and infer their findings in an abstract
and global manner (Boydell & Ferguson, 2012; Smith, Flowers, & Larkin, 2009). In this
study, I collected and analyzed data from a group of individuals and generalized the
findings to a much broader population (the midsouthern United States). I analyzed the
effect the independent variables (age, gender, ethnicity, individual emotional and
physical abilities, types of domestic violence exposure, and frequency of domestic
violence exposure) had on the dependent variable (resilience).
The qualitative approach was not appropriate for this study. Qualitative studies
are idiographic in nature becuase researchers use this approach to gain individual
perspectives of specific phenomena (Creswell, 2009; Pang, 2010a, 2010b). Furthermore,
researchers do not collect qualitative data using psychometrically sound instruments;
variables are not components of this inquiry methodology (Creswell, 2009). The

76
quantitative approach was appropriate for the purpose of this study, in which I aimed to
understand the nomothetic relationships between variables. To examine the relationships
between the independent and dependent variables, I employed step-wise multiple linear
regression.
Methodology
Population
The population of interest were young adults, between the ages of 18 and 25. This
study took place in the BBBS community organization in southwest Texas. Specifically,
the participants in this study were mentees participating in BBBS. The BBBS
organization provides mentoring services to children and young adults to help them
succeed (Herrera, Grossman, Kauh, & McMaken, 2011). This program accepts children and
young adults ages 10–26 from the general population (Herrera, et al), although this study
only included young adults who were between 18–25.
Sampling and Sampling Procedures
I chose convenience sampling as the sampling method for this study. Convenience
sampling is appropriate when it is not feasible to collect a random sample from the entire
population of interest (Creswell, 2009). Because not all members of the population had
an equal chance of selection for the study, the study sample was a convenience sample. In
this study, I used a sample of 118 participants, who were all young adults between the
ages of 18–25. Participants in this study included men and women who were ethnically
diverse (i.e., African American, Hispanic, and Caucasian). Also, participants had to
affirm they could read at a fifth grade reading level.
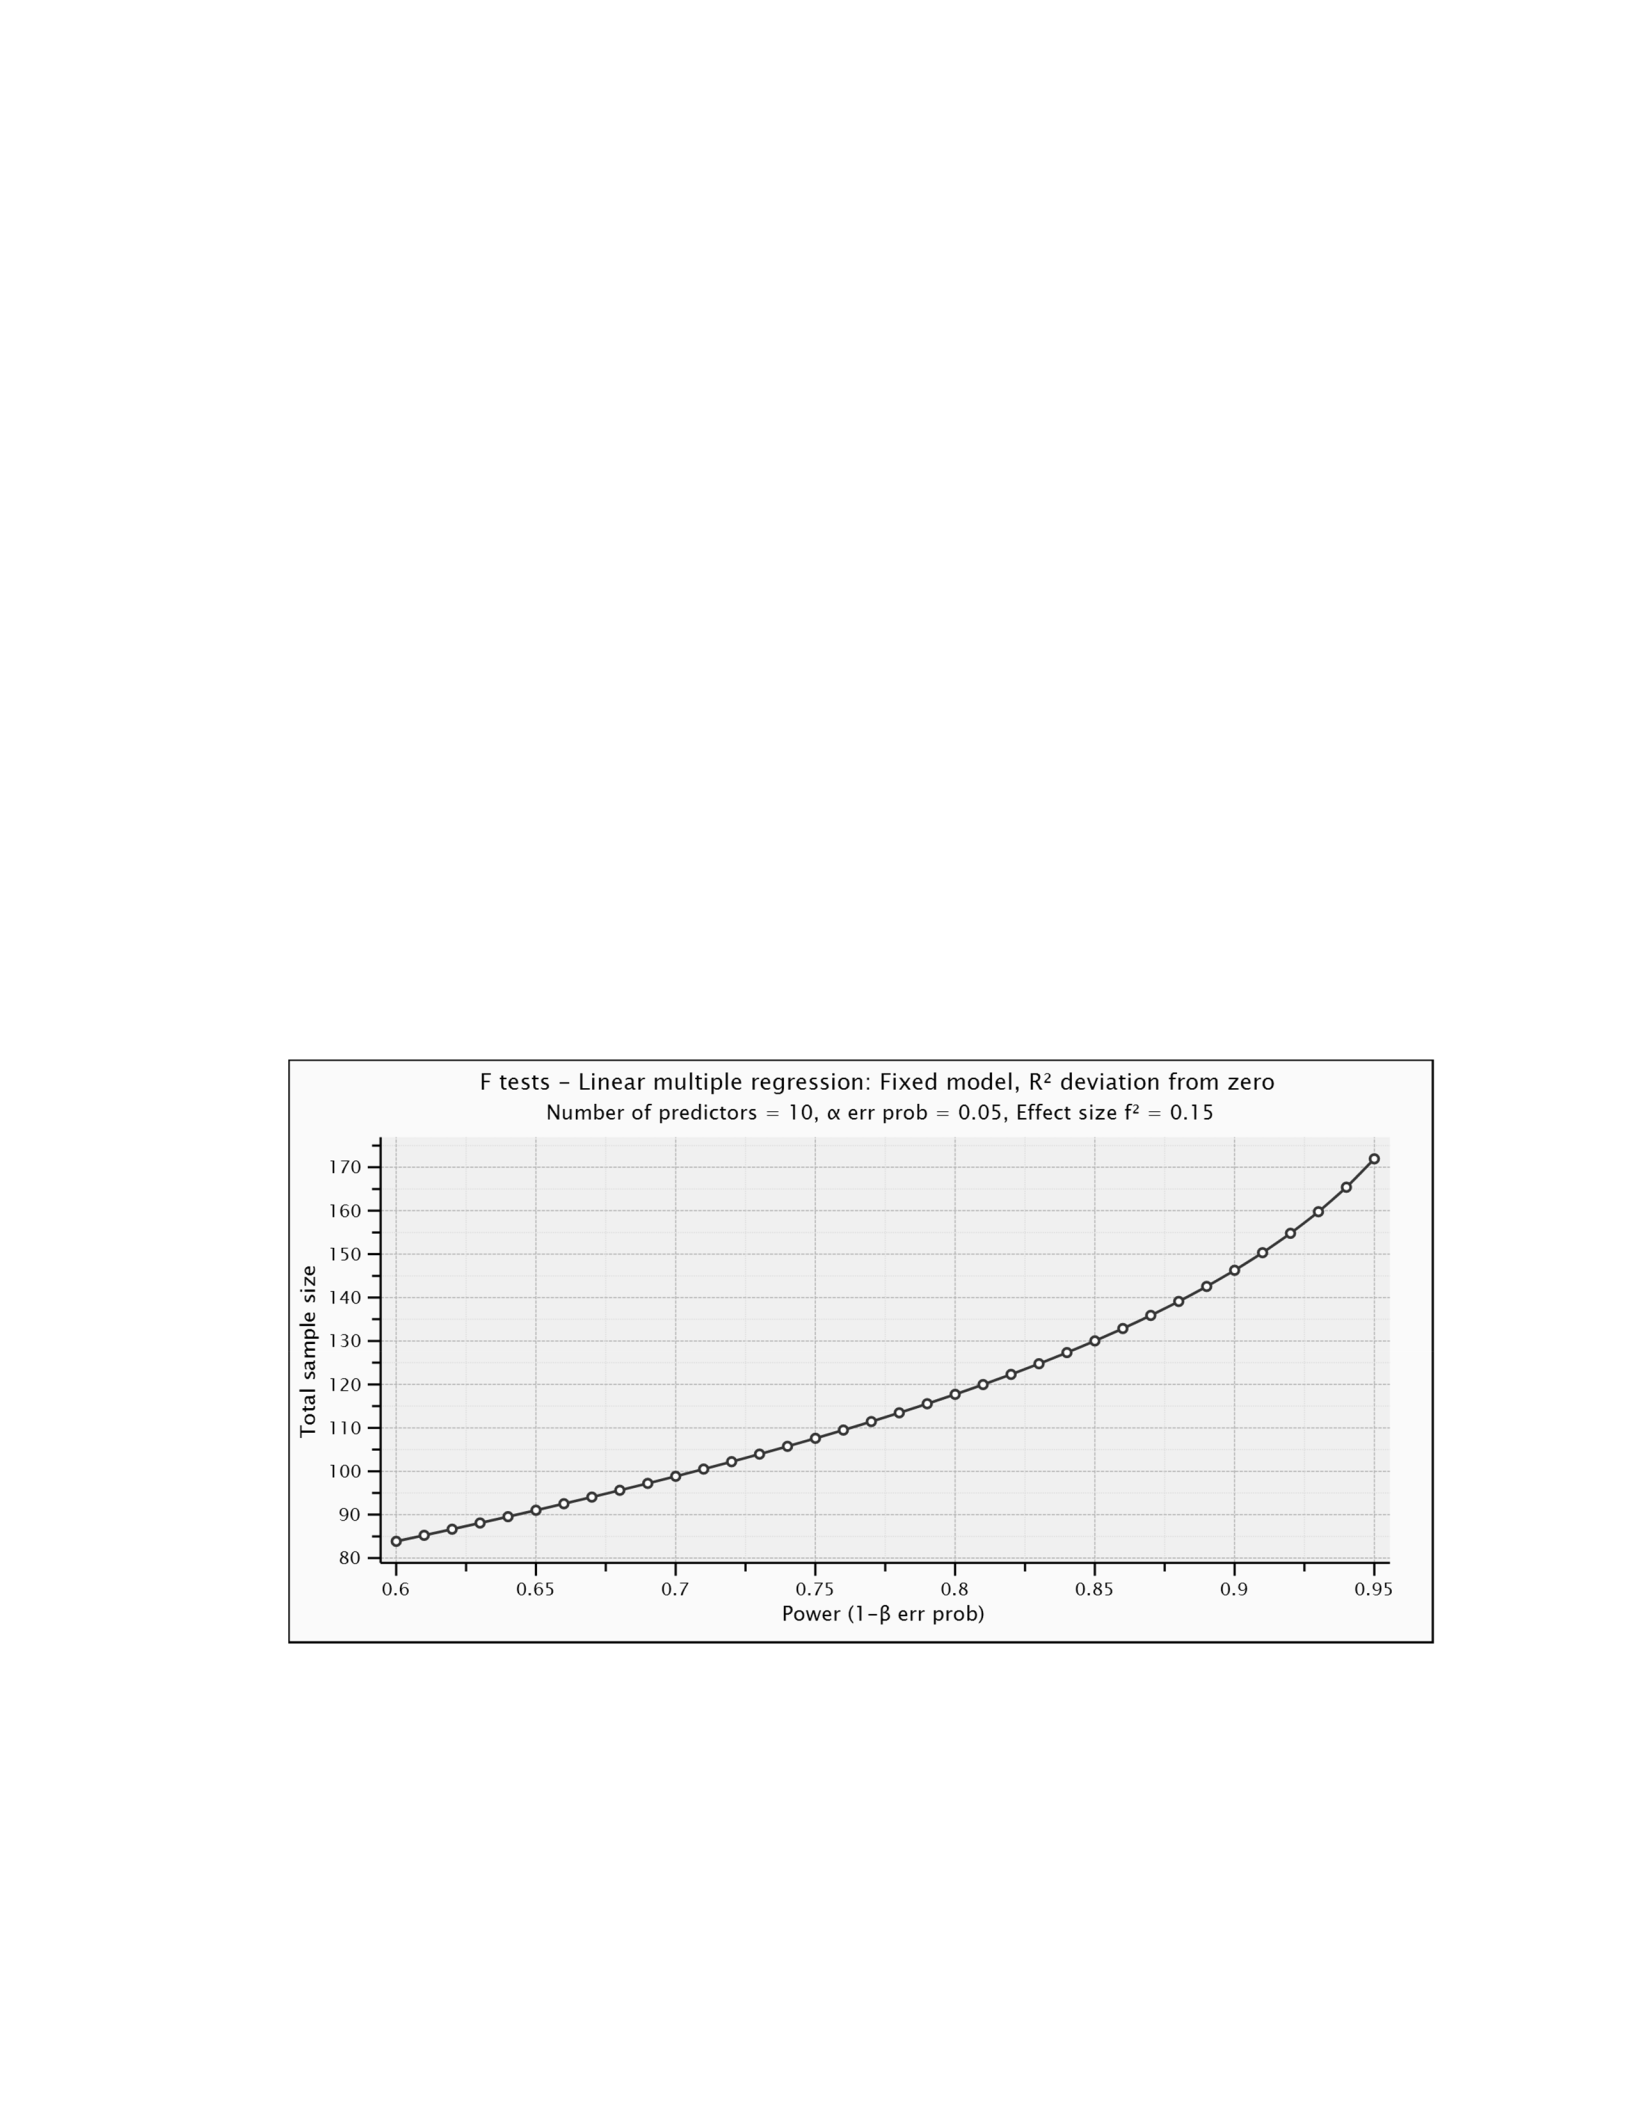
77
To determine an appropriate sample size for the study, I conducted a power
analysis using G*Power software (see Faul, Erdfelder, Buchner, & Lang, 2014). I
conducted an a priori power analysis for a multliple linear regression with 10 predictor
variables; I used a medium effect size (f
2
= .15), an alpha level of .05, and a power level
of .80. The results indicated a minumum sample size of 118 participants to achieve
empirical validity. Increasing the sample size to 172 (assuming a medium effect size and
alpha level of .05) increased the power level to .95. Power refers to the probability of
correctly rejecting the null hypothesis (Creswell, 2009). In most disciplines, a generally
accepted power level is .80 and as the sample size increases, power also increases
(Creswell, 2009). Therefore, I sought between 118 and 172 participants for this study (see
Figure 1).
Figure 1. Power analysis for linear regression with six predictors, an alpha level of .05,
and medium effect size, as a function of sample size.

78
Recruiting Participants and Data Collection
To begin, I secured Walden Institutional Review Board (IRB) approval to conduct
the study using the standards and procedures set forth by Walden University. The initial
research step entailed contacting the director at the BBBS community center study site
via phone calls and face-to-face meetings. The purpose of this initial contact was to (a)
introduce the study; (b) discuss the possibility of recruiting persons within the
organization to participate in the study; and (c) gain an understanding of this community
organization’s policies, which I had to follow. The initial contact allowed me to provide
the community center director with information on the purpose and procedures of the
study. Then, I familiarized myself with the community center requirements regarding
ethical precautions. I wrote a letter of agreement for the organization stipulating the
nature of the research, which granted me permission to recruit potential participants and
conduct survey-based research in the community center. The form had spaces for
signatures and dates from the community center’s director and me.
To recruit participants from the community center, I worked with the directors to
identify and arrange an appropriate method and time for me to distribute a recruitment
flyer (see Appendix A). The BBBS community organization’s policy did not permit
posting flyers in the building, so I identified other arrangements. Specifically, I attended
one of the community center’s meetings to present information about the study. The flyer
included an invitation to attend an optional information meeting and to contact me so I
could explain the research and answer any questions.

79
The community center directors approved times and places for me to conduct the
optional initial information meetings. No designated representatives were required to
conduct the meetings. At the information meetings, I distributed and explained the
informed consent form (see Appendix B). If the attendees elected to participate, I asked
them to read and sign the document at their leisure. I asked them to bring the form with
them when they came to the scheduled data collection meeting.
I scheduled a suitable date, time, and location to conduct the survey collection
after securing the necessary approvals. At this meeting, I collected the informed consent
form, administered the Resiliency Scale (see Appendix B), and administered the CEDV
(see Appendix C). I greeted participants as they arrived, collected each participant’s
informed consent form, and issued them an identification number. Blank copies of the
consent form were also available if a participant arrived without a signed form or did not
attend the initial information meeting. Individuals who were not willing to sign a consent
form were not allowed to participate in the study.
I began data collection by welcoming the participants, briefly explaining the
research study, and explaining my expectations for the participants. I reminded the
participants the information they provided would be held in confidence: their personal
identity and answers would not be linked together and they would not be reported
individually. The participants could withdraw from the study at any point without
repercussions. Following the verbal instructions, when I specifically asked the
participants not to write their names on the two instruments, I distributed the instruments.
Only I administered the instruments; no organization staff participated. The community

80
center had private rooms and had access to an auditorium where most of the
organization’s events take place. The data collection did not interfere with any scheduled
activities because each participant had his or her BBBS meetings outside the
organization’s general program, which is open to the public residing within the county.
The BBBS community center’s policy stipulated the staff members were not allowed to
help in any way during the data collection. It was my sole responsibility to administer the
surveys, collect the data, and store the data securely.
I told the participants to turn their documents face down and leave them on the
table when they completed the survey. I personally thanked each participant as they left
the room. After all instruments were completed, I collected and placed these items in a
sealed envelope and stored the data in a locked file cabinet, accessible only to me prior
to, during, and after data analysis. I ensured confidentiality by using only the participants’
identification numbers instead of their names.
Informed Consent
I informed the individuals participating in this study that participation was strictly
voluntary. As previously noted, I used an informed consent form (see Appendix B) to
adhere to this requirement. Before attending a scheduled meeting to administer the
sruvey, I provided the participants with a copy of the written informed consent form at
one of two preliminary informational meetings. After an individual contacted me and
stated their desire to participate in the research but did not attend one of the meetings, I
provided them with a copy of the informed consent form via the U.S. Mail. Blank forms

81
were available on the day I collected data. I required participant signatures prior to a
participant’s participation in the study.
The informed consent form specified the study was voluntary and participants
were free to withdraw at any time. The consent document also included background
information about the study and how long the questionnaire and instrument would take to
complete. Potential participants were informed of the risks and benefits of the study. My
contact information was available if they had any questions about the study.
Instrumentation and Operationalization of Constructs
Children Exposed to Domestic Violence
In this study, I used the CEDV to assess young adults exposed to domestic
violence as children living in America (Edleson et al., 2007; Margolin & Gordis, 2000;
Tilton-Weaver, 2014). The CEDV is a self-administered instrument designed to collect
data on childhood domestic violence experiences. Children and adults can complete the
instrument (e.g., Makhubela, 2012). Specifically, Makhubela (2012) used the CEDV on a
sample of adolescents and young adults, including undergraduate students ages 18–20.
The authors who created this tool intended to gather an understanding of young adults’
exposure to domestic violence and their ability to set goals for future functioning. I
obtained permission to use the instrument from the authors. This survey appears in
Appendix D.
The CEDV authors identified local domestic violence shelter organizations that
provide services to women and children who have been domestically abused. The authors
gave presentations to key staff members at each agency, inviting them to participate in

82
the scale development project. As a result, four organizations representing five domestic
violence shelters for battered women and children were invited to participate in the
research. Individual agency staff members were asked to identify the guardians of
potential participants. The potential participants were children between 10 and 17 years
of age residing at the community shelter. This designation constituted domestic violence
presence in the home from which these children were coping (Delaney-Black, Covington,
& Sokol, 2006; Mowder, Cummings, & McKinney, 2010; Prince-Embury & Steer,
2010). Three psychometricians and facilities officials examined interrelated themes from
the domestic violence perspective and concluded the results were accurate in terms of age
and situations that were appropriate for the study constructs (Kernic, Monary-Erensdorff,
Koepsell, & Holt, 2005; Kumar, Steer, & Gulab, 2010).
In this study, coefficients measured by Cronbach’s alpha demonstrated a strong
relative internal consistency between α =.74 and α =.76. The results indicate high
reliability to establish a strong test-retest reliability (r =.67) with interrater reliability
results (r =.81) among children’s exposure to domestic violence (Richters & Martinez,
1990; Van Wyk, 2011). This exposure affected behavior, school performance, and future
functioning (Delaney-Black, Covington, & Sokol, 2006; Richter & Martinez, 1993).
Researchers have also demonstrated the reliability of the CEDV using a sample of
adolescents and young adults (including individuals as old as 20 years) with a Cronbach’s
alpha of .85.
In this section, validity refers to a tool’s ability to accurately measure what it
purports to measure. Four residential treatment organizations, representing five domestic

83
violence exposure shelters were recruited to participate in the study to accurately obtain
the resilience constructs (Edleson, Shin, & Johnson, 2007; Hopf, 2010; Kernic, Monary-
Erensdorff, Koepsell, & Holt, 2005; Leong & Austin, 2006; Pallant, 2009). Participants
from these shelters consisted of 65 children and adolescents. Among those recruited were
children between the ages of 10 and 16 years old. I gave the guardians of the children a
list detailing the instructions, expectations, confidentiality, risks, benefits, and purpose of
the study (Edleson et al., 2007; Kleinman, Adams, Kashdan, & Riskind, 2013).
The CEDV consists of six subscales that measure: violence, exposure to violence
at home, exposure to violence in the community, involvement in violence, risk factors,
and other victimization (see Appendix C). I used the exposure to violence at home
subscale to measure the overall level of domestic violence. Specifically, this subscale
represented the theoretical implications of a microsystem, representing family violence. I
used the violence subscale to measure the frequency of domestic violence exposure. I
used the exposure to violence in the community subscale to measure types of violence
exposure. Finally, I used the other victimization subscale to measure emotional and
physical abilities.
The exposure to violence at home subscale is comprised of Questions 1–10 on the
CEDV. Each item has two parts. The first part requires a yes or no response. If the
individual answered “no”, I moved to the next question. If the individual answered “yes”,
I addressed the second part of the question by selecting as many of the five choices
available. A total score is derived by summing the total number of choices selected on the
second part of Questions 1–10. The total score can range from 0–50. Higher scores

84
indicate a higher level of exposure to violence in the home. This scale yielded a
quantitative score, or interval data. An example question from the scale is, “How often
has your mom’s partner hurt, or tried to hurt, a pet in your home on purpose?”
Demographic Information
Embedded within Part III of the CEDV instrument (Items 38–40; Appendix C) are
three items measuring the demographic variables of participants. Specifically, the items
ask the participants their age, gender, and ethnicity. This information serves as potential
predictor variables.
Resilience Scale
The Resilience Scale is a 25-item Likert scale instrument that measures resilience,
the dependent variable in this study. The resilience measures five characteristics of
resilience: self-reliance, purposeful life, equanimity, perseverance, and existential
aloneness. Wagnild and Young (1991) derived these five invariant essences from a
qualitative inquiry. The purpose of their study was to explore resilience through two
targeted populations: women who successfully moved on with their lives after a
significant loss (i.e., loss of spouse, health, or employment) and women whose spouses
suffered from Alzheimer’s’ disease. I obtained permission to use the instrument from the
authors. The instrument is in Appendix D.
Internal consistency reliability coefficients, measured by Cronbach’s alpha, have
ranged from .85 to .95 across a diverse sample. Examples include: healthy adults (.92), a
depressed population (.92), sheltered battered women (.94), mothers with pre-school
children (.85), elderly Korean Women (.95), and military wives (.86; Humphreys, 2003;

85
Lee et al., 2007; Monteith & Ford-Gilboe, 2002; Schachman, Lee, & Lederman, 2004;
Wagnild, 2009; Wagnild & Young, 1993)
Validity refers to the ability of a measurement to accurately measure what it
purports to measure (Wagnild, 2009). As mentioned earlier, reserachers developed the
Resilience Scale from themes derived from a qualitative study (Wagnild & Young, 1993).
The researchers identified five interrelated components that constituted resilience. Two
psychometricians and nurse practitioners reviewed the interrelated themes and
determined the instrument accurately depicted resilience constructs.
Convergent validity refers to the degree of correlation between measures of the
same trait. Convergent validity exists if the observed correlation coefficients are high.
Conversely, discriminant validity refers to the degree in which two measures differ in
measuring a specific trait. Discriminant validity exists when the a reasearcher observes
low correlation coefficients. To assess convergent and discriminant validity, I used items
from the Health Promoting Lifestyle Profile (HPLP), a psychometrically sound
assessment of health promoting behaviors. The HPLP has six subscales: stress
management, health responsibility, nutrition, exercise, self-actualization, and
interpersonal support. I used a sample of 776 middle-aged to older adults in the analyses.
I expected higher correlations (convergent validity) between the Resilience Scale
responses and the corresponding HPLP domains. I expected lower correlations between
Resilience Scale domains, and the exercise and nutrition domains of the HPLP. The
analyses supported acceptable convergent and discriminant properties. Table 1 depicts
the results of these analyses.

86
Table 1
Correlation Coefficients between the RS and HPLP Domains
Scale
Self-
Actualization
Health
Responsibility
Nutrition
Exercise
Inter-
Personal
Support
Stress
Management
RS 0.62 0.37 0.33 0.26 0.49 0.46
Concurrent validity refers to the degree to which scores on a new measure (i.e.,
Reslience Scale) are related to scores from a criterion measure administered at the same
time. I assessed concurrent validity using the Life Satisfaction Survey, the Philadelphia
Geriatric Center Morale Scale, and the Beck Depression Inventory. I hypothesized a
positive correlation would be found between the Resliency Scale, Life Satisfaction
Survey, and the Philadelphia Geriatric Center Morale Scale. I hypothesized a negative
correlation would be found between the Resliency Scale and the Beck Depression
Inventory. These hypotheses were supported. Table 2 depicts the correlation coefficients
of these analyses.
Table 2
Correlation Coefficients
Life Satisfaction Morale Depression
Resilience Scale 0.37 0.32 -0.41
For each item, the participants used a 7-point Likert scale, ranging from 1
(strongly disagree) to 7 (strongly agree). Summing the scores for each of the 25-item
responses derives a total score, or interval data. The total score can range from 25–175.

87
Higher scores indicate a higher level of resilience. All items were worded positively,
therefore, there was no reverse scoring of any items. An example item on the instrument
was, “I usually take things in stride.”
Data Analysis Plan
I entered and analyzed data using SPSS version 22 (IBM, 2012). First, I screened
the data for missing values. I removed any participants who did not complete the entire
demographic questionnaire and research instrument. Likewise, I examined the
demographic and instrument calculated scores for outliers. When I identified an outlier, I
removed it. For the purposes of this study, I defined outliers as values larger than 3.29
standard deviations from the mean (Stevens, 2009).
After cleaning the data, I conducted the analysis using multiple linear regression
to pursue the previously stated research question and associated hypotheses:
Research Question: Do domestic violence, age, gender, ethnicity, individual
emotional and physical abilities, types of domestic violence exposure, and
frequency of domestic violence exposure, when in linear combination,
significantly predicts resilience, as measured by the Resilience Scale among
young adults in the Midsouth region of the United States?
Null Hypothesis (H
0
): Domestic violence, age, gender, ethnicity, individual
emotional and physical abilities, types of domestic violence exposure, and
frequency of domestic violence exposure, when in linear combination do not
significantly predict resilience, as measured by the Resilience Scale among young
adults in the Midsouth region of the United States.

88
Alternative Hypothesis (H
1
): Domestic violence, age, gender, ethnicity, individual
emotional and physical abilities, types of domestic violence exposure, and
frequency of domestic violence exposure, when in linear combination
significantly predicts resilience, as measured by the Resilience Scale among
young adults in the Midsouth region of the United States.
I conducted stepwise multiple linear regression to test the null hypothesis and
answer the research question and hypothesis. Because I wanted to predict a quantitative
outcome variable, multiple linear regression was appropriate (Creswell, 2009; Oransky,
Hahn, & Stover, 2013). Resilience was based on a set of ten predictor variables: domestic
violence experienced at home, gender, age, three categories of ethnicity, emotional
abilities, physical abilities, types of domestic violence exposure, and frequency of
domestic violence exposure. I considered a factorial ANOVA, but I determined it would
be an inappropriate technique for developing exploratory predictive models.
The resiliency scale, the CEDV, and age yield participant data on an interval, or a
continuous, level of measurement. Gender and ethnicity are categorical, or nominal,
variables. To use these two variables as predictors, I transformed them into dummy
variables suitable for use in multiple linear regression. Gender was a dichotomous
variable, coded as 0 (male), and 1 (female). The ethnicity variable consisted of four
ethnic groups or categories: African American, Caucasian, Hispanic, and other. Table 3
presents how I coded the dummy variables for ethnicity.

89
Table 3
Dummy Coding for the Ethnicity Variable
Dummy Variable 1 Dummy Variable 2 Dummy Variable 3
African American 0 0 0
Hispanic 1 0 0
White 0 1 0
Other 0 0 1
I used stepwise multiple linear regression. The stepwise method accounts for all
the independent (predictor) variables to determine the best final predictive equation. I
entered variables into the model one at a time, starting with the variable with the most-
predictive power (highest correlation). I added or subtracted subsequent variables from
the equation. This entering-or-removing process continued until I entered or discarded all
the potential predictor variables, resulting in the optimum prediction equation based on R,
multiple correlation. I evaluated variables based on what each added to the prediction of
the dependent variable that was different from the predictability provided by the other
predictors (Tabachnick & Fidell, 2012). I used the default values in SPSS for entry (p =
.05) and removal (p = .10). I used the F test to assess whether the resting set of
independent variables collectively predicted the dependent variable. After each step in the
regression analysis, I examined the R
2
, the multiple coefficient of determination, to assess
the additional predictive power each additional variable added to the model. I reported
the final R
2
value and used to to indicate how much variance in the dependent variable
was accounted for by the set of independent variables. I included a t-test in the analysis to
determine the significance of each predictor variable’s beta coefficients.

90
I assessed the assumptions underlying multiple linear regression: linearity,
homoscedasticity and absence of multicollinearity. I explain this in detail in Chapter 4.
Linearity refers to the existence of a straight line relationship between the predictor
variables and the criterion variable. Homoscedasticity refers to the idea that scores are
normally distributed around the regression line. I assessed linearity and homoscedasticity
by examining scatter plots. The absence of multicollinearity means the predictor variables
are not strongly related to one another, which I assessed using variance inflation factors
(VIF). If a VIF value is greater than 10, this finding indicates multicollinearity (Stevens,
2009).
Threats to Validity
External Validity
In this research, I studied a defined population; therefore, the results of this study
may not be generalized to other populations within or outside the target organization.
However, the results can provide baseline data for future research. Results from this
study may allow speculative inferences for other similar organizations, but such
inferences must be viewed as tentative. Future findings must be validated through
appropriate research protocols.
It is conceivable that the findings from this study may carry unintended weight. It
was my responsibility to exercise caution when reporting findings or making evaluative
statements about the results. In addition to answering the stated research question, I also
considered the social, political, and human implications of this study when I reported the
findings. Furthermore, accepted professional ethical principles, such as those set forth by

91
the American Psychological Association (2010), guided but did not restrict my right to
view and use the appropriate reporting standards in the best interests of my conscience
and for the benefit of the scientific community.
Internal Validity
Statistical conclusion validity. Threats to statistical conclusion validity
constitute conditions that impair the likelihood of accuracy in detecting an empirical
relationship (Leong & Austin, 2006). Failure to address these threats may compromise
the results and lead either a Type I or a Type II error. These threats include sample size,
reliability of the instruments, and violations of the assumptions regarding multiple linear
regression. I address these threats, as they pertained to this study, as follows.
Sample size. I used the appropriate sample size, as previously described, to
ensure the study had enough power to detect a significant predictive relationship, if one
existed in the population. I addressed this threat by conducting a power analysis to
determine the ideal sample size.
Reliability of instruments. Invalid or unreliable instruments are a threat to
internal research validity. Although I previously described the instruments were as being
valid and reliable, I calculated Cronbach’s alpha for the CEDV and Resilience Scale to
determine their reliability as it pertained to this sample. A coefficient of .70 or higher
indicates acceptable reliability (Pallant, 2009). I compared the obtained coefficients to
this standard.
Regression assumptions. The results of the multiple linear regression can be
affected by violations of the assumptions underlying the procedure. These assumptions

92
include multicollinearity, outliers, normality, linearity, homoscedasticity, and
independence of the residuals. Multicollinearity refers to a high degree of correlation
between each of the independent variables. This means the correlation between any two
of the independent variables should not exceed .70 (Pallant, 2009). I examined this
assumption through a review of collinearity diagnostics produced from the SPSS
procedure. Collinearity diagnostics indicate problematic correlations that may not be
apparent in a correlation matrix. I examined the VIF indicators. If a VIF value is higher
than 10, the results may be problematic (Pallant, 2009). When I identified
multicollinearity, I retained the predictor(s) with the highest correlation for the analysis
and removed or combined the other predictor(s), when appropriate.
I assessed outliers, normality, linearity, homoscedasticity, and independence of
the residuals using a normal probability plot of the regression standardized residual and
the scatterplot created in the regression SPSS procedure (Pallant, 2009). I made
appropriate data corrections (i.e., dummy variable transformations and deletion of
outliers) prior to inferential statistical testing.
Ethical Procedures
Avoiding coercion and preserving human rights are universal precautions
researchers take when using human participants in a research study (IRB Forum, 2008). I
accepted the responsibility to maintain ethical research procedures and eliminate
potentially harmful emotional reactions, physical harm, or psychological effects
experienced by the participants. Although psychological harm is difficult to define, I
identified and removed any suspected harmful effects that may have been caused by

93
participating in the study. Furthermore, ethical standards dictate before obtaining consent
from participants, it is the researcher’s obligation to inform the participants of the
research purpose, potential benefits, and anything that may affect participants’
willingness to participate. Reserachers must also answer any participants’ questions to
assure participant comprehension. I designed the research protocol for this study to
address these standards. Before consent was obtained from the participants, I secured the
necessary approvals from the previously identified organization to conduct research in
that setting (see Appendix E; IRB Forum, 2008).
Because this research contains no manipulated independent variable(s) and used
survey research methodology, there was minimal risk for the voluntary participants.
Additionally, if participants experienced any psychological or emotional distress during
the study, I provided them contact information for appropriate counseling services.
I obtained approval from the Walden University IRB prior to collecting any data.
As required by the IRB, I removed all the participant identification information, such as
names, prior to the data analysis to ensure participants’ confidentiality, as I promised
during participant recruiting.
I placed the collected data in a sealed envelope and stored it in a locked file
cabinet before removing it for analysis. Subsequently, I kept electronic data (e.g., SPSS
data files) on my personal computer in a password protected folder. I will destroy all
electronic and paper data five years after the study was completed.

94
Summary
In this chapter, I outlined the design for the research study, which was
correlational and quantitative in nature. I discussed the characteristics of the sample, the
description of the study site, and the procedures for sampling and data collection. I
provided the psychometric properties, including internal reliability, convergent validity,
and concurrent validity of the instruments used in the study. Each of instruments have
been shown to have strong reliability and validity, and were therefore appropriate for use
in the study. In this chapter, I delineated the data analysis, and included rationale and
procedures for using stepwise linear regression to address the research question. I
considered potential threats to internal and external validity, and provided several
strategies to combat these threats. I also included the protocol for ethical considerations
for the protection of human subjects; I took every step necessary to protect participants
from undue risk.

95
Chapter 4: Results
Introduction
The purpose of this study was to explore whether domestic violence, age, gender,
ethnicity, individual emotional abilities, physical abilities, types of domestic violence
exposure, and frequency of domestic violence exposure could, individually or in linear
combination, adequately predict resiliencey among young adults in the Midsouth region
of the United States. The specific research question was:
Do domestic violence, age, gender, and ethnicity, individual emotional and
physical abilities, types of domestic violence exposure, and frequency of domestic
violence exposure, when in linear combination, significantly predicts resilience,
as measured by the resiliency scale among young adults in the Midsouth region of
the United States?
H
0
: Domestic violence, age, gender, ethnicity, individual emotional and physical
abilities, types of domestic violence exposure, and frequency of domestic violence
exposure, when in linear combination, do not significantly predict resilience as
measured by the RS among young adults in the Midsouth region of the United
States.
H
1
: Domestic violence, age, gender, ethnicity, individual emotional and physical
abilities, types of domestic violence exposure, and frequency of domestic violence
exposure, when in linear combination, significantly predicts resilience as
measured by the RS among young adults in the Midsouth region of the United
States.
96
This chapter contains the results of the data analysis I conducted to address the
research question and hypotheses. In this chapter, I describe the data collection and
demographic characteristics of the sample. Then, I present the results of the data analysis.
This chapter will conclude with a summary.
Data Collection
I collected the data for this study in June 2017. A total of 118 young adults from
BBBS completed the survey. No participants were excluded because of missing data and
I did not identify any outliers in the data. Table 4 displays descriptive statistics for the
categorical demographic variables. The age range of the participants was 18–22 years (M
= 19.99, SD = 1.42). The sample was approximately split between men (n = 60, 50.8%)
and women (n = 58, 49.2%). The largest proportion of participants indicated their
ethnicity as Black (n = 35, 29.7%).
Table 4
Descriptive Statistics for Categorical Demographic Variables
Variable n %
Gender
Male 60 50.8
Female 58 49.2
Ethnicity
White 34 28.8
Black 35 29.7
Latino 32 27.1
Other 17 14.4
97
In Table 5, I display the descriptive statistics for the summated scores
representing domestic violence, frequency of domestic violence exposure, types of
domestic violence, emotional abilities, physical abilities, and resilience. Specifically, I
used the exposure to violence at home subscale of the CEDV instrument to measure the
overall level of domestic violence. I used the violence subscale of the CEDV to measure
the frequency of domestic violence exposure. I used the exposure to violence in the
community subscale of the CEDV to measure the types of violence exposure (i.e., degree
of community violence exposure). I measured participant’s emotional and physical
abilities using the other victimization subscale of the CEDV. I measured resilience using
the overall score on the resiliency sclae. I computed the summated scores by summing
the responses to the items corresponding to each variable.
Table 5
Descriptive Statistics for Summated Scores
Variable M SD
Domestic violence 25.32 5.16
Frequency of domestic violence exposure
16.58 4.47
Type of domestic violence exposure 15.58 3.69
Emotional and physical abilities 6.69 2.77
Resilience 128.54 30.86
Results
To answer the research question and hypotheses, I conducted a stepwise multiple
linear regression. Reslience, domestic violence, emotional and physical abilities, types of
domestic violence exposure, and frequency of domestic violence exposure yielded data

98
on an interval, or continuous, level of measurement. Gender and ethnicity were
categorical, or nominal, variables. To use these two variables as predictors, I transformed
them into dummy variables. Gender was coded as 0 (male) and 1 (female). Ethnicity
consisted of four categories: Black, White, Latino, and other. I dummy-coded these
variables and Black served as the reference category. Becuase there was no logic for
doing otherwise, I used the default values in SPSS for stepwise predictor entry (p = .05)
and removal (p = .10) in the regression equation.
I assessed the assumptions of linearity, homoscedasticity, and absence of
multicollinearity prior to analysis. Linearity means there is a straight line relationship
between the predictor variables and the criterion variable (Leong & Austin, 2006; Pallant,
2009). Homoscedasticity means scores are normally distributed about the regression line
Leong, et al). I assessed linearity and homoscedasticity by examining scatter plots (see
Figure 2, Figure 3). The data did not strongly deviate from the normal line (Figure 2), and
the data were approximately evenly distributed around zero (Figure 3). Therefore, the
assumptions of linearity and homoscedasticity were met. The absence of multicollinearity
means the predictor variables are not strongly correlated with each other, which assessed
using VIF (Plancherel & Bolognini, 2012). Stevens (2009) noted VIF values over 10
suggest the presence of multicollinearity. In the present study, the VIF values were below
10, so this assumption was met.
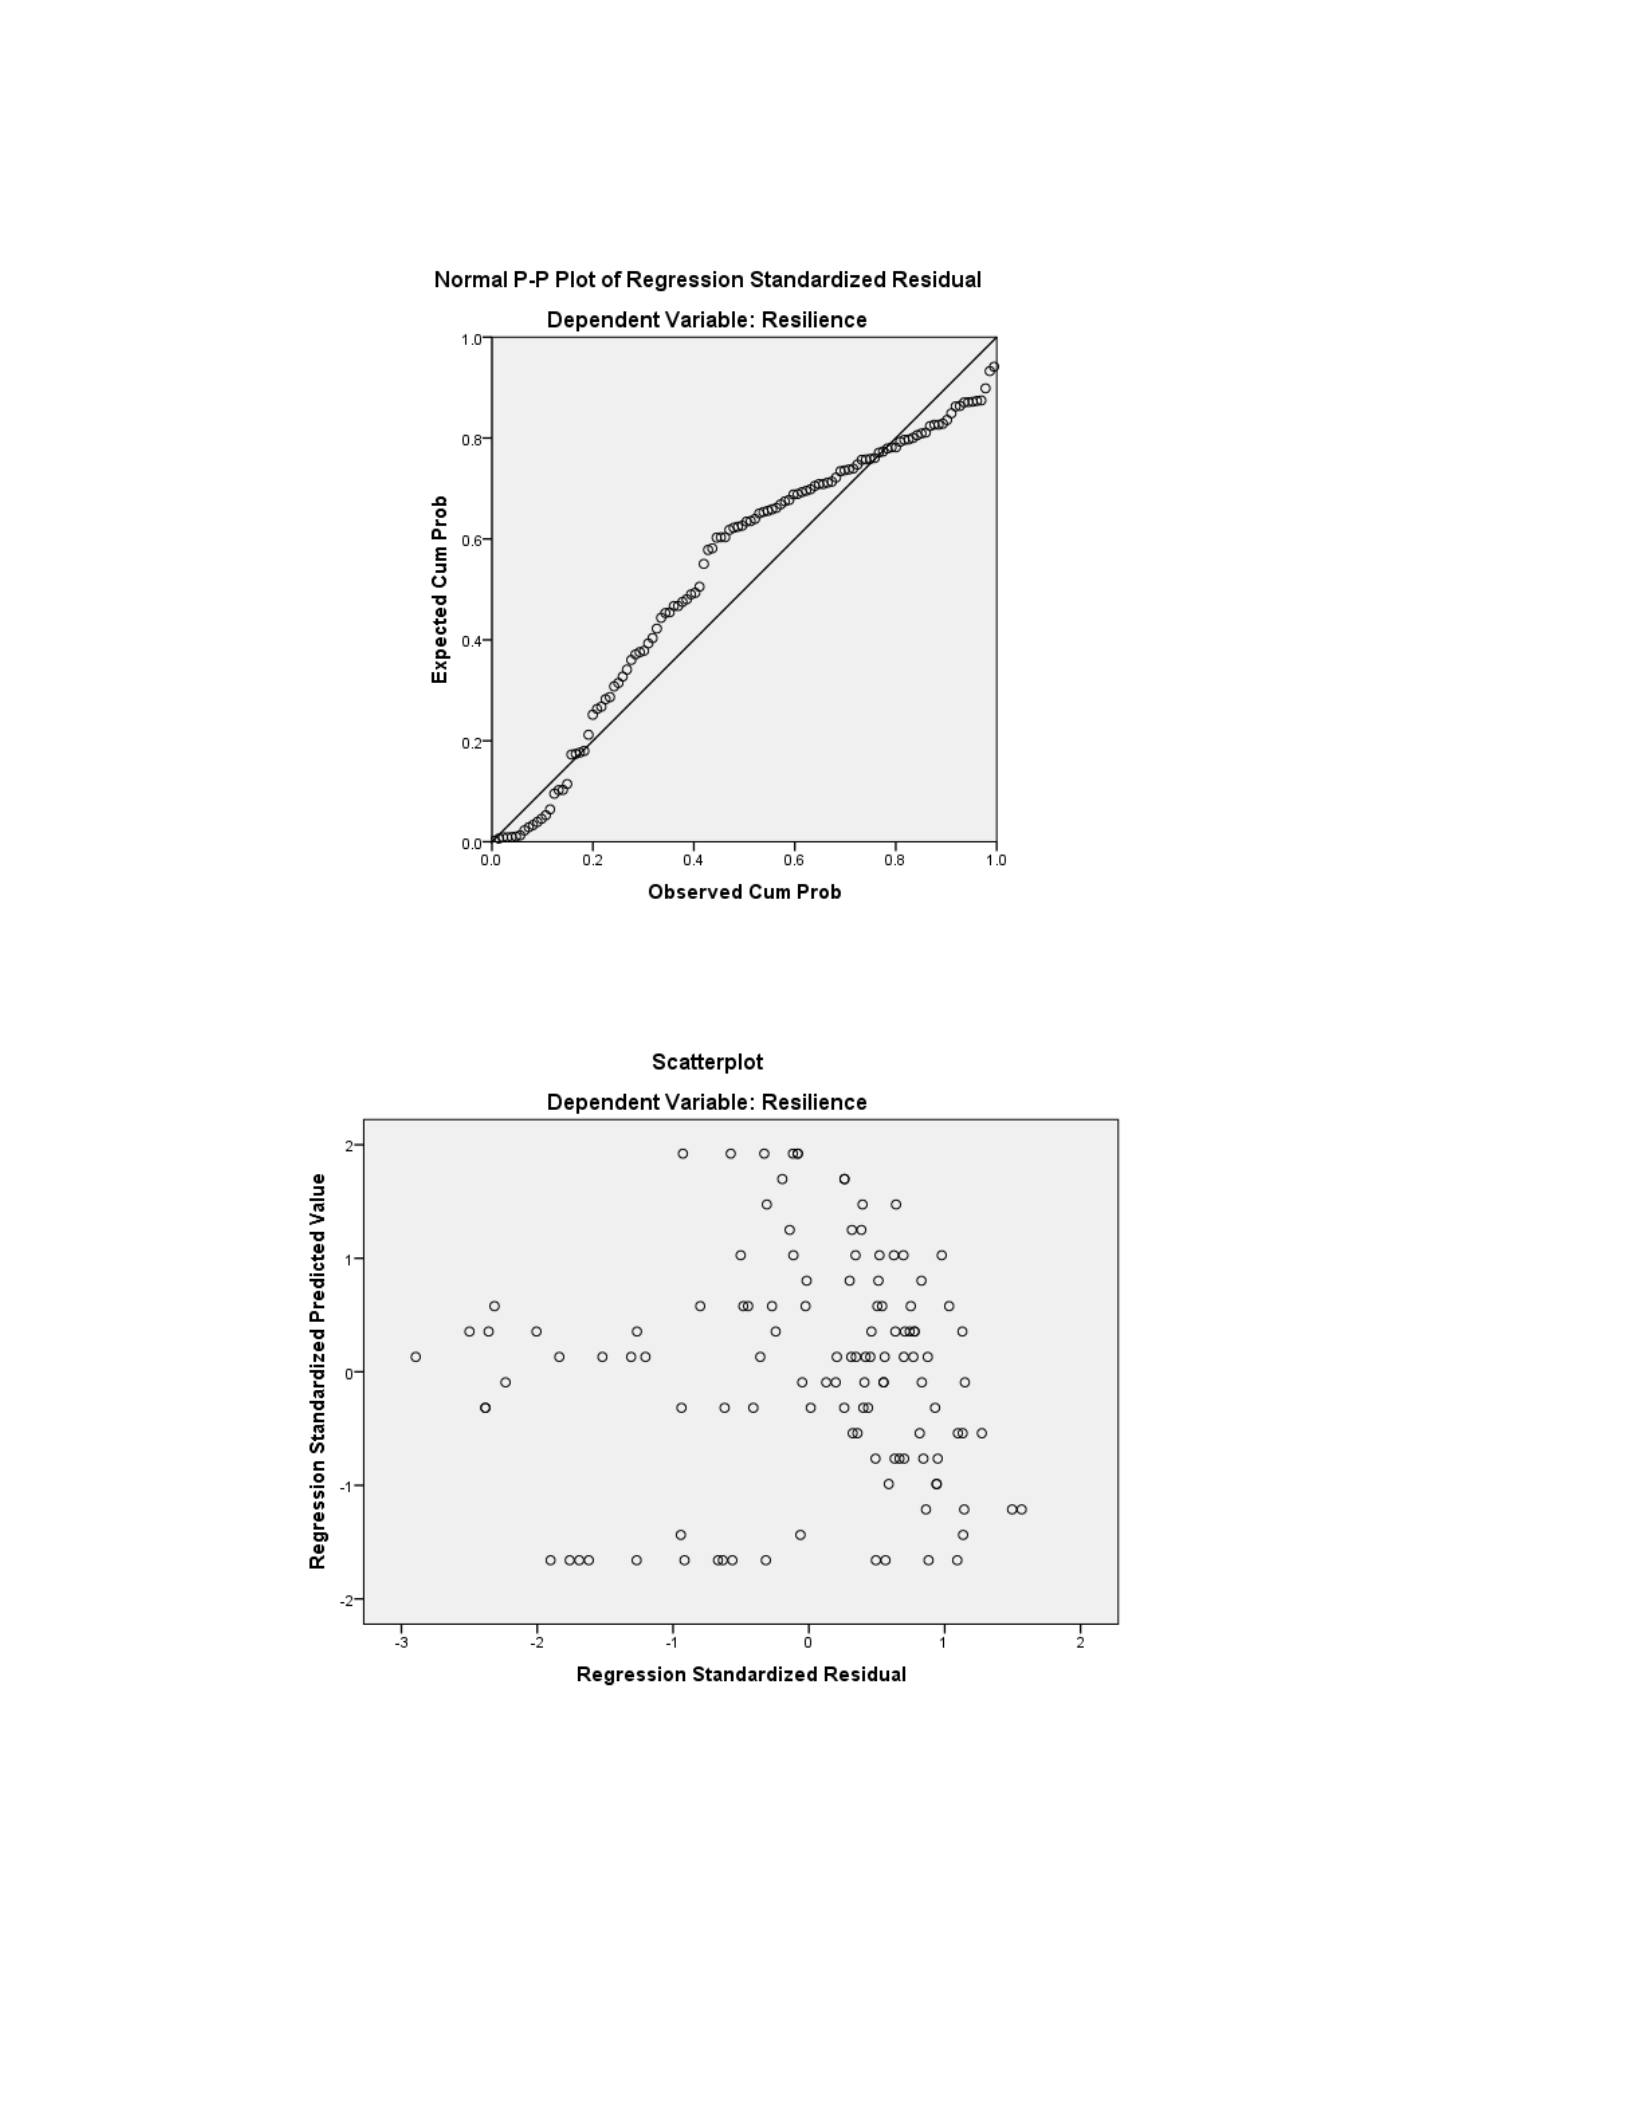
99
Figure 2. Normal P-P scatter plot for stepwise multiple linear regression.
Figure 3. Scatter plot of residuals versus predicted values for stepwise multiple linear
regression.

100
Using the stepwise algorithm, I arrived at the final model in one step. In the final
model, I only included the frequency of domestic violence exposure. I excluded the other
predictor variables: domestic violence, age, gender, ethnicity, emotional and physical
abilities, and types of domestic violence exposure. The final model determined by the
stepwise algorithm was significant: F(1, 116) = 22.25, p < .001, R
2
= .16. This indicated
the final model, consisting of one predictor, significantly predicted resilience in this
sample. Therefore, the H
0
was rejected. The R
2
value indicated the final model accounted
for 16% of the variability in resilience. I present the results of the regression model in
Table 6. Frequency of domestic violence exposure was a significant negative predictor (B
= -2.77, p < .001), indicating participants who scored higher on frequency of domestic
violence exposure tended to have lower resilience scores.
Table 6
Final Stepwise Multiple Linear Regression Model Predicting Resilience
Predictor B Std.
Error Beta t Sig. VIF
Frequency of domestic
violence exposure
-2.77 0.59 -0.40 -4.72 < .001 1.00
Note. F(1, 116) = 22.25, p < .001, R
2
= .16.
Summary
This chapter contained the results of the data analysis I conducted to address the
research question. The research question asked the following: do domestic violence, age,
gender, and ethnicity, individual emotional and physical abilities, types of domestic
violence exposure, and frequency of domestic violence exposure, when in linear

101
combination, significantly predicts resilience as measured by the resiliency scale among
young adults in the Midsouth region of the United States? I conducted a stepwise
multiple linear regression analysis to address this question. The results of the analysis
were significant, so the H
0
was rejected. The final model determined by the stepwise
algorithm included one predictor: frequency of domestic violence exposure. This was a
significant negative predictor, indicating participants with higher frequency of domestic
violence exposure tended to have lower resilience. Chapter 5 contains a discussion of
these findings in relation to previous literature. I also discuss the implications and
directions for future research in Chapter 5.

102
Chapter 5: Conclusions, Summary, and Recommendations
Introduction
Domestic violence has significant negative influences on the 1.5 million young
adults in the United States who witness and experience it each year (Childhood Domestic
Violence Association, 2014). However, resilience allows these youths to grow into
caring, competent, and confident young adults (Black et al., 2015; Masten & Powell,
2003; Rutter, 1980; Werner, 2004). Therefore, it is beneficial for researchers to
investigate factors that predict resilience. Previous researchers have suggested exposure
to domestic violence may increase resilience (Anderson et al., 2012). In addition,
demographic factors that may influence resilience levels include age (Ali et al., 2015;
Garthe et al., 2014; Jan et al., 2015); gender (Black et al., 2015; Dietz et al., 2014); and
ethnicity (Danquah et al., 2010; Flores et al., 2014; Holland & Gill, 2010; McKnown-
Johnson & Rhodes, 2013; Zautra et al., 2010). Research had not been completed
regarding these factors in conjunction and how they interact to predict resilience among
young adults.
The purpose of this study was to explore whether domestic violence, age, gender,
ethnicity, individual emotional and physical abilities, types of domestic violence
exposure, and frequency of domestic violence exposure could adequately predict
resilience among young adults in the Midsouth region of the United States. In this study,
I examined responses to the CEDV instrument from a sample of 118 participants who
were members of BBBS in southwest Texas. The stepwise multiple linear regression
revealed frequency of domestic violence exposure predicted resilience. Specifically, the

103
more frequently participants experienced domestic violence, the less likely they were to
have a high resiliency score. Chapter 5 includes an interpretation of the findings in the
study and the study limitations. The chapter also includes a discussion of the
recommendations for further research and the implications of the findings. Lastly, I
dicuss the conclusions along with social change implications.
Interpretation of the Findings
Young adults exposed to domestic violence often experience negative social,
emotional, and cognitive long-term outcomes (Job et al., 2012; Löckenhoff et al., 2012;
Sorbello et al., 2012; Williams & Steinberg, 2011). The adverse effects associated with
domestic violence are consistent with Bronfenbrenner’s ecological theory. Domestic
violence occurs in the mesosystem and fundamentally shapes the individuals’ subsequent
interactions in the mesosystem and exosystem (Holland et al., 2015), continuing as the
affected individuals reach adulthood (Black et al., 2015; Goodrum et al., 2012).
Conversely, resilience forms when access to mesosystem or exosystem resources
counteract negative microsystem factors; for example, this might include close
relationships with extended families, friends, or role models (De Los Reyes et al., 2013;
Dondero, 1997; Garthe et al., 2014; Grossman & Tierney, 1998; O’Donohue & Ferguson,
2006; Wolkow & Ferguson, 2001).
The results of this study indicated that among the sample of 118 participants, only
one of the multiple predictor variables significantly predicted resilience: frequency of
domestic violence exposure. Frequency of domestic violence exposure was a significant
negative predictor (B = -2.77, p < .001) and predicted 16% of the variance in resilience

104
scores. The frequency of domestic violence exposure negatively predicted resilience. The
more frequently participants experienced domestic violence, the less likely they were to
have high resilence scores. I examined the frequency of domestic violence exposure
using the violence subscale of the CEDV, which asks participants to identify, on a scale
ranging from never to always, how frequently they experience various violent situations.
The results indicated different types of domestic violence did not predict resilience;
moreover, I did not identify a relationship between resilience and any of the demographic
predictor variables.
The results of the present study were inconsistent with some results in the
literature. For example, Anderson et al. (2012) determined a sample of women exposed to
domestic violence had higher than average resilience scores. Anderson et al. (2012) did
not examine the frequency of exposure to domestic violence as a specific variable;
however, the results of Anderson et al.’s (2012) study suggested those who experienced
domestic violence had higher resilience scores. These data were inconsistent with the
findings of the present study, which indicated more exposure to domestic violence
resulted in lower resilience scores.
Many researchers have focused on young adults’ psychological and behavioral
responses; however, researchers should focus their attention on young adults’ social
environments and the frequency of exposure to predict if resilience will occur (Widom &
Wilson, 2015). The results of this study related to frequency of domestic violence are
consistent with studies indicating domestic violence exposure in the young adults’
environments negatively influences resilience development. For example, Kassis et al.

105
(2013) determined, through multiple linear regression, that negative experiences such as
domestic violence, poor parenting, and alcohol/drug abuse reduced resilience among a
sample of middle-school students from Austria, Germany, Slovenia, and Spain (N =
5,149). Similarly, researchers have noted negative family environments deter resilience
development (Carroll, 2006; Garthe et al., 2014; Gerard & Buehler, 1999; Waldon et al.,
2001). Flores et al. (2014) noted the family environment and the protective factors within
a microsystem were determinants of resilience development. Thus, the findings of this
study supported the findings of previous researchers regarding frequent domestic
violence exposure in the mesosystem. This exposure adversely affected the participants’
abilities to form resilience.
The finding that there was no relationship between demographic variables and
resilience development was mixed in relation to how it corresponded to recent literature.
Similar to the findings of the present study, Kassis et al. (2013) found no relation
between demographic variables and resilience development, instead emphasizing the
importance of structural variables. However, previous researchers supported the influence
of demographics on resilience formation, including age (Ali et al., 2015; Garthe et al.,
2014; Jan et al., 2015); gender (Black et al., 2015; Dietz et al., 2014); and ethnicity
(Danquah et al., 2010; Flores et al., 2014; Holland & Gill, 2010; McKnown-Johnson &
Rhodes, 2013; Zautra et al., 2010).
The findings of the present study did not indicate a predictive relationship
between gender and resilience development. Some reserachers determined gender
influenced resilience development (Black et al., 2015; Dietz et al., 2014). However, the

106
findings from the present study did not support that claim. Previous researchers indicated
males were more likely than females to display adverse outcomes from domestic violence
exposure, such as aggression instead of resilience (Hughes, 2015; Rosenbaum &
O’Leary, 2010; Wexler, 2015). Furthermore, there was an indication that male young
adults were more likely than females to experience physical violence directed toward
themselves, which researchers suggested may influence their responses to domestic
violence exposure (Margolin & Gordis, 2015; Miller, Handal, Gilner & Cross, 2015;
Schwarz & Getter, 2015; Straus et al., 2014; Widom, 2014). However, the results of the
present study were consistent with the results found by other researchers who did not
determine a relationship between gender and resilience formation. For example, Solberg
et al. (2007) found no significant differences between young adult males and young adult
females with respect to resilience formation.
Regarding ethnicity and resilience, this study included a roughly equal
representation of Black (N = 35), Latino (N = 32), and White (N = 34) participants, and a
significant representation of other (N = 17) participants, whereas other studies on
ethnicity included a sample that represented the demographic breakdown in the United
States (Danquah et al., 2010; Flores et al., 2014; Holland & Gill, 2010; McKnown-
Johnson & Rhodes 2013; Zautra et al., 2010). The participants’ ethnic breakdowns
reflected the BBBS convenience sample in southwest Texas. Surveying larger
proportions of ethnic minorities might provide more representation; however, the results
may not be representative of the population of the United States.

107
The results of the present study seemed to contradict the idea that age is a
significant predictor. The results related to frequency of domestic violence exposure and
resilience may further illuminate previous results regarding the relationship between age,
resilience, and domestic violence. Ali et al. (2015) and Rosenthal and Wilson (2003)
determined the earlier in life participants were exposed to domestic violence, the less
likely they were to form resilience. Garthe et al. (2014) found early removal from a
domestic violence situation increased the likelihood that a youth would develop
resilience. This finding could have been the result of early and prolonged exposure to
domestic violence, which would result in greater perceived frequency of domestic
violence incidences because the youth would have been exposed to such behavior
throughout his or her childhood. Therefore, the findings of this study further explain
previous correlations between age of exposure, domestic violence, and a lack of
resilience formation.
The results of the present study indicated that young adults exposed to domestic
violence were statistically prone to exhibiting low resiliency and had tendencies to utilize
aggressive methods to respond to external threatening issues and this can also be based
on age, and culture of the individual.
However, because of the limited sample size of this study, one cannot make
generalizations regarding over or under representation of domestic violence about one
ethnicity. From this study findings, it is shown that young adults, especially the African
American participants, reported low resilience compared to White participants. It is not
clear why Hispanic participants had higher resilience levels than their counterparts. This

108
could be a result of cultural differences, such as how each culture perceives the term
domestic violence, and the values associated with the term and beliefs (Coie & Dodge,
2014; Edleson, Shin, & Johnson Armendariz, 2008).
Limitations of the Study
The main limitation of this study was the small sample size of young adults from
a limited geographic region. Individuals in the population and the resulting sample
resided in the Midsouth region of the United states and did not represent the population
of individuals affected by domestic violence in other regions of the country.
Consequently, I cannot use the results obtained from this study to generalize the U.S.
population, only the Midsouth region.
In this study, I focused on violence young adults primarily observe at home and
within their social environments. As previously noted, influences beyond the
microsystem, including the exosystem and the mesosystem may also influence resilience
development. These might include mentorships and coaching (De Los Reyes et al., 2013;
Dondero, 1997; Garthe et al., 2014; Grossman & Tierney, 1998; O’Donohue & Ferguson,
2006; Wolkow & Ferguson, 2001) or the removal of an individual from a domestic
violence situation (Garthe et al., 2014). One limitation of the study involved microsystem
factors as the primary focus of the chosen variant.
I used the CEDV tool to gather data for this study. The CEDV is an established
tool for assessing domestic violence exposure (Edleson, et al). However, the results of
this study are limited to the accuracy of the tool.

109
Recommendations
The results of this study significantly contributed to the body of scholarly data by
identifying a predictor variable for resilience; however, additional research is required to
develop a model with a higher predictive value. Although the findings of the present
study were significant (R
2
= .16), it is important for future researchers to seek out
conjunctive variables to more accurately predict resiliency. From the findings of this
study, I believe scholars will find it helpful to continue studies on the effects of frequent
domestic violence exposure on young adults’ resilience. Specifically, I recommend a
more granular look, using the CEDV, to see which specific behaviors on the violence
subscale most influence resilience scores. Future researchers should seek alternative
variables within an ecosystem, such as mentors, coaches, and child protective service
interventions, to see how these resources influence resilience development.
Researchers should consider further study on this topic, including the insights of
future findings, this study did not provide because of limitations and sample size. Until
the time of this study, researchers frequently employed homogenous demographic
samples. Many researchers conducted studies using only people who identified as women
or identified as a specific ethnicity (Black et al., 2015). In this study, I focused on
participants of all genders and a wide range of ethnicities to gain a better understanding
of individual resilience formation and adaptation. I recommend researchers continue to
gain a wide range of experiences from varied samples. I also recommend replicating the
present study with a national sample to test the generalizability of the findings.

110
Furthermore, longitudinal studies may help researchers better understand the long-term
predictors of resilience as young adults exposed to domestic violence enter adulthood.
Implications
Although frequent exposure to domestic violence can reduce resilience, previous
researchers indicated exposure to a community, role models, and early removal from a
domestic violence situation can increase an individual’s resilience (Ali et al., 2015;
Garthe et al., 2014; Rosenthal & Wilson, 2003). Therefore, the results of the present
study, in conjunction with previous research, indicate the necessity for further research.
Also, practitioners, lawmakers, social leaders, and support staff in schools to identify
domestic violence situations and to intervene with positive support, such as BBBS, or in
extreme circumstances, to remove the child from the home.
Researchers have shown if violence happens once, it usually reoccurres with a
greater consequence (Ali et al., 2015; Beam, Gil-Rivas, Greenberger, & Chen, 2012;
Garthe et al., 2014; Jan et al., 2015; Plancherel & Bolognini, 2012; Storksen, Roysamb,
Moum, & Tambs, 2010). The results of the present study indicated frequent exposure to
domestic violence predicted decreased resilience. Therefore, it is important to put a crisis
plan in place for the caregiver and the victims. A crisis plan should consist of a safe plan
that includes community organizations, lawmakers, policies, friends, and relatives to help
reinforce the safety plan in the best interest of the young adult. To deal with young
adults’ emotional abuse and home life experiences requires adequate intervention
programs such as counselling, role modeling adults, adequate accomodation,
transportation, and financial support. However, to promote adequate resources and to

111
execute the safety plan, local and governmental agencies must establish collaborative
responses to produce a positive response outcome.
For therapists, facility workers, and lawmakers, this finding indicates an
awareness of the effects of frequent domestic violence exposure as a priority for the
development of youth in American society. Therapists and community agencies must
support trauma-informed education. Community agencies must develop asset-based
research and information that will influence policy and practices affecting young adults
exposed to domestic abuse. Social agencies and their employees must be able to establish
basic education for parents, teachers, and counselors to be more aware of the influence of
frequent adult violent behaviors in the home. Similarly, case workers in government and
private agencies might use the findings from this study as a tool to advocate for
lawmakers to acknowledge and expedite laws protect parents and families in the best
interests of children, namely by reducing the frequency of domestic violence experiences.
The results further imply the need for widescale programs to support youths who
have been exposed to frequent domestic violence. These programs may help youths
improve coping skills based on their previous exposures to violence. The providers
working with this population must have adequate resources to train volunteers in this
issue and promote the message of hope despite the negative effects of violence on young
adults’ transitions to adulthood. Individuals who have been exposed to domestic violence
need technical assistance, encouragement, and guidance related to resilience adaptation
for future functioning.

112
The results of this study provide practitioners, lawmakers, and social leaders with
vital information about the effects of domestic violence on young adults They also
provide future researchers and clinicians with a significant opportunity to better
understand the issues that affect young adults’ responses to resiliency. Researchers have
focused on asset-based evidence, which suggests prior experiences may have provided
young adults with protective factors that allowed them to maintain resilience despite
adversity (Damant et al., 2010; DeForge, Belcher, O’Rourke, & Lindsey, 2005;
D’Imperio et al., 2000; Resnick, Bearman, Blum, & Bauman, 1997; Rutter, 1985).
However, the present study indicates researchers must acknowledge the significant
influence on resiliency that frequent exposure to domestic violence may cause. For
individuals with high domestic violence exposure, researchers and clinicians should focus
on and empathize with the adverse effects such exposure may have had on the person’s
ability to form a resilient response. Lastly, these findings can be used as a baseline for
data collections regarding young adults’ experiences with domestic violence. This
exposure can allow behavior modification toward self-actualization.
Implications for Social Change
Young adults who are exposed to frequent domestic violence may not have the
ability to use effective methods to resolve issues, therefore continuing the cycle of abuse.
Among young adults exposed to domestic violence, microsystem situations have
conditioned their information processing system to respond to threats with violence rather
than using ignoring tatics or walking away. For example, if young adults have witnessed
physical, financial, and emotional abuse by one of their parents or have seen a parent

113
slapping the other parent, throwing things or objects to the wall, choking, stabbing, or
shooting in the home, they are more likely to use learned behaviors to respond to threats
(Edleson et al., 2007; Horn, Williams, & Scott, 2002; Lesch & Ursula, 2000; Pagelow,
1990; Solberg et al., 2007).
When a young adult is exposed to a negative experience such as domestic
violence as a child, the individual can either develop resilience or have an adverse
reaction. Adverse reactions include negative social, cognitive, and behavioral issues,
which young adults may carry into adulthood (Ali et al., 2015; Garthe et al., 2014; Jan et
al., 2015). The results of the present study implied frequent exposure to violence affects
young adults adversely. Carlson (2006) reported high rates of poverty are attributed to
direct exposure to family violence and community violence. Similarly, Horowitz,
Margolin, and Gordis (2000) indicated 50% of children exposed to domestic violence met
the criteria for PTSD. These researchers suggested there is a need for community social
supports and available resources to minimize the effects of living in violent homes and
neighborhoods. Exposure to domestic violence directly affects young adults in the short-
term, but also indirectly affects young adult’s development and behaviors in the long-
term (Horowitz et al., 2000). The present study supported this assertion by demonstrating
frequent exposure to domestic violence predicted low resilience.
To foster resilience, practitioners must understand predictive factors that influence
resilience development. To effect social change, individuals must seek methods to reduce
the frequency of domestic violence exposure. Individuals can accomplish this through
interventions to remove the child from the home (Garthe et al., 2014) or providing

114
alternative community support (Ali et al., 2015). Through these interventions, individuals
may avoid the long-term effects of domestic violence exposure, including mental illness,
aggression, and low self-esteem (Clauzade, 2009; Sorbello et al., 2012; Williams &
Steinberg, 2011).
Conclusion
Previous researchers focused on adolescent behavior, rather than the microsystem
surrounding the adolescents. They also focused on predictive factors that increased or
decreased resilience, provided an incomplete view of the influence of domestic violence
on youth’s development of resilience (Beam, Gil-Rivas, Greenberger, & Chen, 2012;
Edleson et al., 2007; Edleson, Shin, & Johnson Armendariz, 2008; LaLiberte et al., 2010;
Plancherel & Bolognini, 2012; Shin & Edleson, 2007; Storksen, Roysamb, Moum, &
Tambs, 2010). I designed the present study to gain insight into specific factors that would
predict resilience. Specifically, the purpose of this study was to explore whether domestic
violence, age, gender, ethnicity, individual emotional and physical abilities, types of
domestic violence exposure, and frequency of domestic violence exposure could
adequately predict resilience among young adults in the Midsouth region of the United
States.
I performed a multiple linear regression of the responses to the CEDV from a
sample of 118 participants, who were members of BBBS in southwest Texas. The results
revealed that the frequency of domestic violence exposure negatively predicted
resilience, indicating participants with higher frequency of domestic violence exposure
tended to have lower resilience, compared to participants with fewer exposures. This

115
finding suggested continued, frequent exposure to domestic violence significantly
influenced an individual’s ability to develop resiliency. Results indicate the need for
continued vigilance from researchers, clinicians, child protective services, and lawmakers
to reduce children’s frequency of exposure to domestic violence. Furthermore, the results
indicated the need for further examination of environmental protective factors that may
affect resilience development, according to Bronfenbrenner’s ecological model. By
discovering factors that predict resilience, whether positive or negative, stakeholders can
target interventions and develop policies to eradicate the harmful social and
psychological effects of domestic violence on children.

