


1
Section 1: Foundation of the Study and Literature Review
Child mortality is a public health problem. Also referred to as under-5
mortality, it is defined as the death of children under the age of 5 (Winking,
2016). Fortunately, under-5 mortality rates have been on the decline
(Ezbakhe & Pérez Foguet, 2020), but the problem persists. According to
Ezbakhe and Pérez Foguet (2020), in the 1990s, a reported 12,500,000
children under the age of 5 died globally. By 2018, that number had
decreased to 5,300,000 per year. However, this number is still considered
excessive, specifically in areas such as sub-Saharan Africa (World Health
Organization [WHO], 2022). The number has also been consistent over the
last 5 years. In 2020, half of the under-5 deaths occurred within the 1st
month postbirth (WHO, 2022). Many of the causes of under-5 deaths are
preventable. Infectious diseases, preterm birth complications, birth
asphyxia/trauma, pneumonia, diarrhea, and malaria are among the leading
causes (United Nations Children's Fund [UNICEF], 2023; WHO, 2022).
This study focused on Sierra Leone’s child mortality and potential
causes as it relates to water and sanitation. In this section, I provided a
synopsis of this study, including a summary of prior research in the field that
offers an understanding of the problem. The purpose of the study and the

2
study's three research questions (RQs) and associated hypotheses were
stated. The guiding theoretical framework for the study, Urie
Bronfenbrenner’s (1970) socioecological model (SEM), was discussed. I also
addressed the nature of the study and give an overview of the literature
search strategy. An extensive literature review precedes definitions of
important study terms. Study assumptions, scope and delimitations, and
limitations were assessed. To conclude, I discussed the significance of this
study, summarized key points made in the section, and provided a transition
to Section 2.
Background
Sub-Saharan Africa has the highest under-5 mortality rate in the world
(Gaffan et al., 2023). In 2020, sub-Saharan Africa accounted for 2,700,000
under-5 mortality deaths; this equated to over half the under-5 reported
deaths globally (Gaffan et al., 2023; Waddington et al., 2023). One of the
presumed contributing causes is water, sanitation, and hygiene (WASH).
WASH interventions are an important part of life, specifically in early
childhood and development (Headey & Palloni, 2019; Russell & Azzopardi,
2019; Sharma Waddington & Cairncross, 2021). According to Waddington et
al. (2023), in low- and middle-income countries (LMICs) like Sierra Leone

3
WASH is associated with high levels of global disease including respiratory
illness and diarrhea.
Previous researchers have conducted cross-sectional studies on WASH
and its impacts on mortality and stunting (Headey & Palloni, 2019).
Although strong associations were determined in some studies, weak and no
associations were also been found. Headey and Palloni (2019) asserted that
information on the connection between WASH interventions and child health
outcomes is limited and, in some cases, inconsistent. Cluster randomized
control trials and case-control studies showed strong associations between
WASH and incidents of diarrhea, but those same studies showed no
significance between WASH and child stunting, they noted. According to
my review of the literature, no researcher to date has examined the effect of
WASH variables and child mortality in Sierra Leone.
Problem Statement
The situation that prompted the search of the literature is that,
according to UNICEF (n.d.-c), in 2021, 2,200,000,000 people did not have
access to safe drinking water, 3,000,000,000 did not have access to
handwashing facilities with soap, and half the world’s population did not
have access to safe sanitation. UNICEF (n.d.-b) also reported that just 16%

4
of Sierra Leone’s population had access to basic sanitation services.
Therefore, the impetus for conducting this study was the alarming statistics
presented by UNICEF revealing that a significant portion of the global
population lacks access to safe drinking water, handwashing facilities with
soap, and adequate sanitation services. In Sierra Leone, the majority of the
population lack access to basic sanitation services. The lack of water
infrastructure highlights a pressing social issue.
Purpose of the Study
The purpose of this quantitative study was to examine how variables
related to access to toilet facilities and safe drinking water in rural and urban
areas of Sierra Leone affect child mortality. The independent variables I used
were source of water, water treatment type, type of toilet facility, location of
toilet facility, whether the toilet facility was shared, area (rural, urban),
education of head of household, sex of head of household, and wealth index.
The dependent variable was child mortality. In this study, I aimed to
contribute an understanding of the dynamics at play, ultimately informing
evidence-based interventions and policy recommendations.

5
Research Questions and Hypotheses
The RQs and hypotheses underpinning this quantitative cross-sectional
study included
RQ1: Is there an association between location of water source, location
of toilet facility, area, wealth index, education and sex of head of household
on child mortality in Sierra Leone?
H01: There is no association between location of water source, location
of toilet facility, area, wealth index, education, and sex of head of
household on child mortality in Sierra Leone.
HA1: There is an association between location of water source,
location of toilet facility, area, wealth index, education, and sex of
head of household on child mortality in Sierra Leone.
RQ2: Is there an association between the location of water source,
location of toilet facility and child mortality in Sierra Leone, when
controlling the factors of sex of head of household, wealth index, education,
and area?
H02: There is no association between the location of water source,
location of toilet facility and child mortality in Sierra Leone, when

6
controlling the factors of sex of head of household, wealth index,
education, and area.
HA2: There is an association between the location of water source,
location of toilet facility and child mortality in Sierra Leone, when
controlling the factors of sex of head of household, wealth index,
education, and area.
RQ3: Is there an association between water treatment type, number of
households using toilet facility and child mortality in Sierra Leone, when
controlling the factors of sex of head of household, wealth index, education,
and area?
H03: There is no association between water treatment type, number of
households using toilet facility and child mortality in Sierra Leone,
when controlling the factors of sex of head of household, wealth
index, education, and area.
HA3: There is an association between water treatment type, number of
households using toilet facility, and child mortality in Sierra Leone,
when controlling the factors of sex of head of household, wealth
index, education, and area.

7
Theoretical Framework
The theoretical framework I used for this study was the SEM. The
SEM conceptualizes health on a large scale, focusing on multiple factors that
impact health outcomes at several levels (Agency for Toxic Substances and
Diseases Registry, 2015). For this study, aspects of both physical and social
well-being were analyzed. This model looks at how health can be affected by
individual, community, and physical environments (Agency for Toxic
Substances and Diseases Registry, 2015). The SEM clarifies that individual
interactions with other people and the environment impact health decisions
and, potentially, outcomes (University of Minnesota School of Public Health,
2021). The framework thus aligned with the study's purpose and nature as it
conceptualizes health comprehensively, incorporating physical, mental, and
social well-being, and explores the interplay between individuals;
communities; and their physical, social, and political environments, all of
which affect health decisions.
Factors in the Social Ecological Method
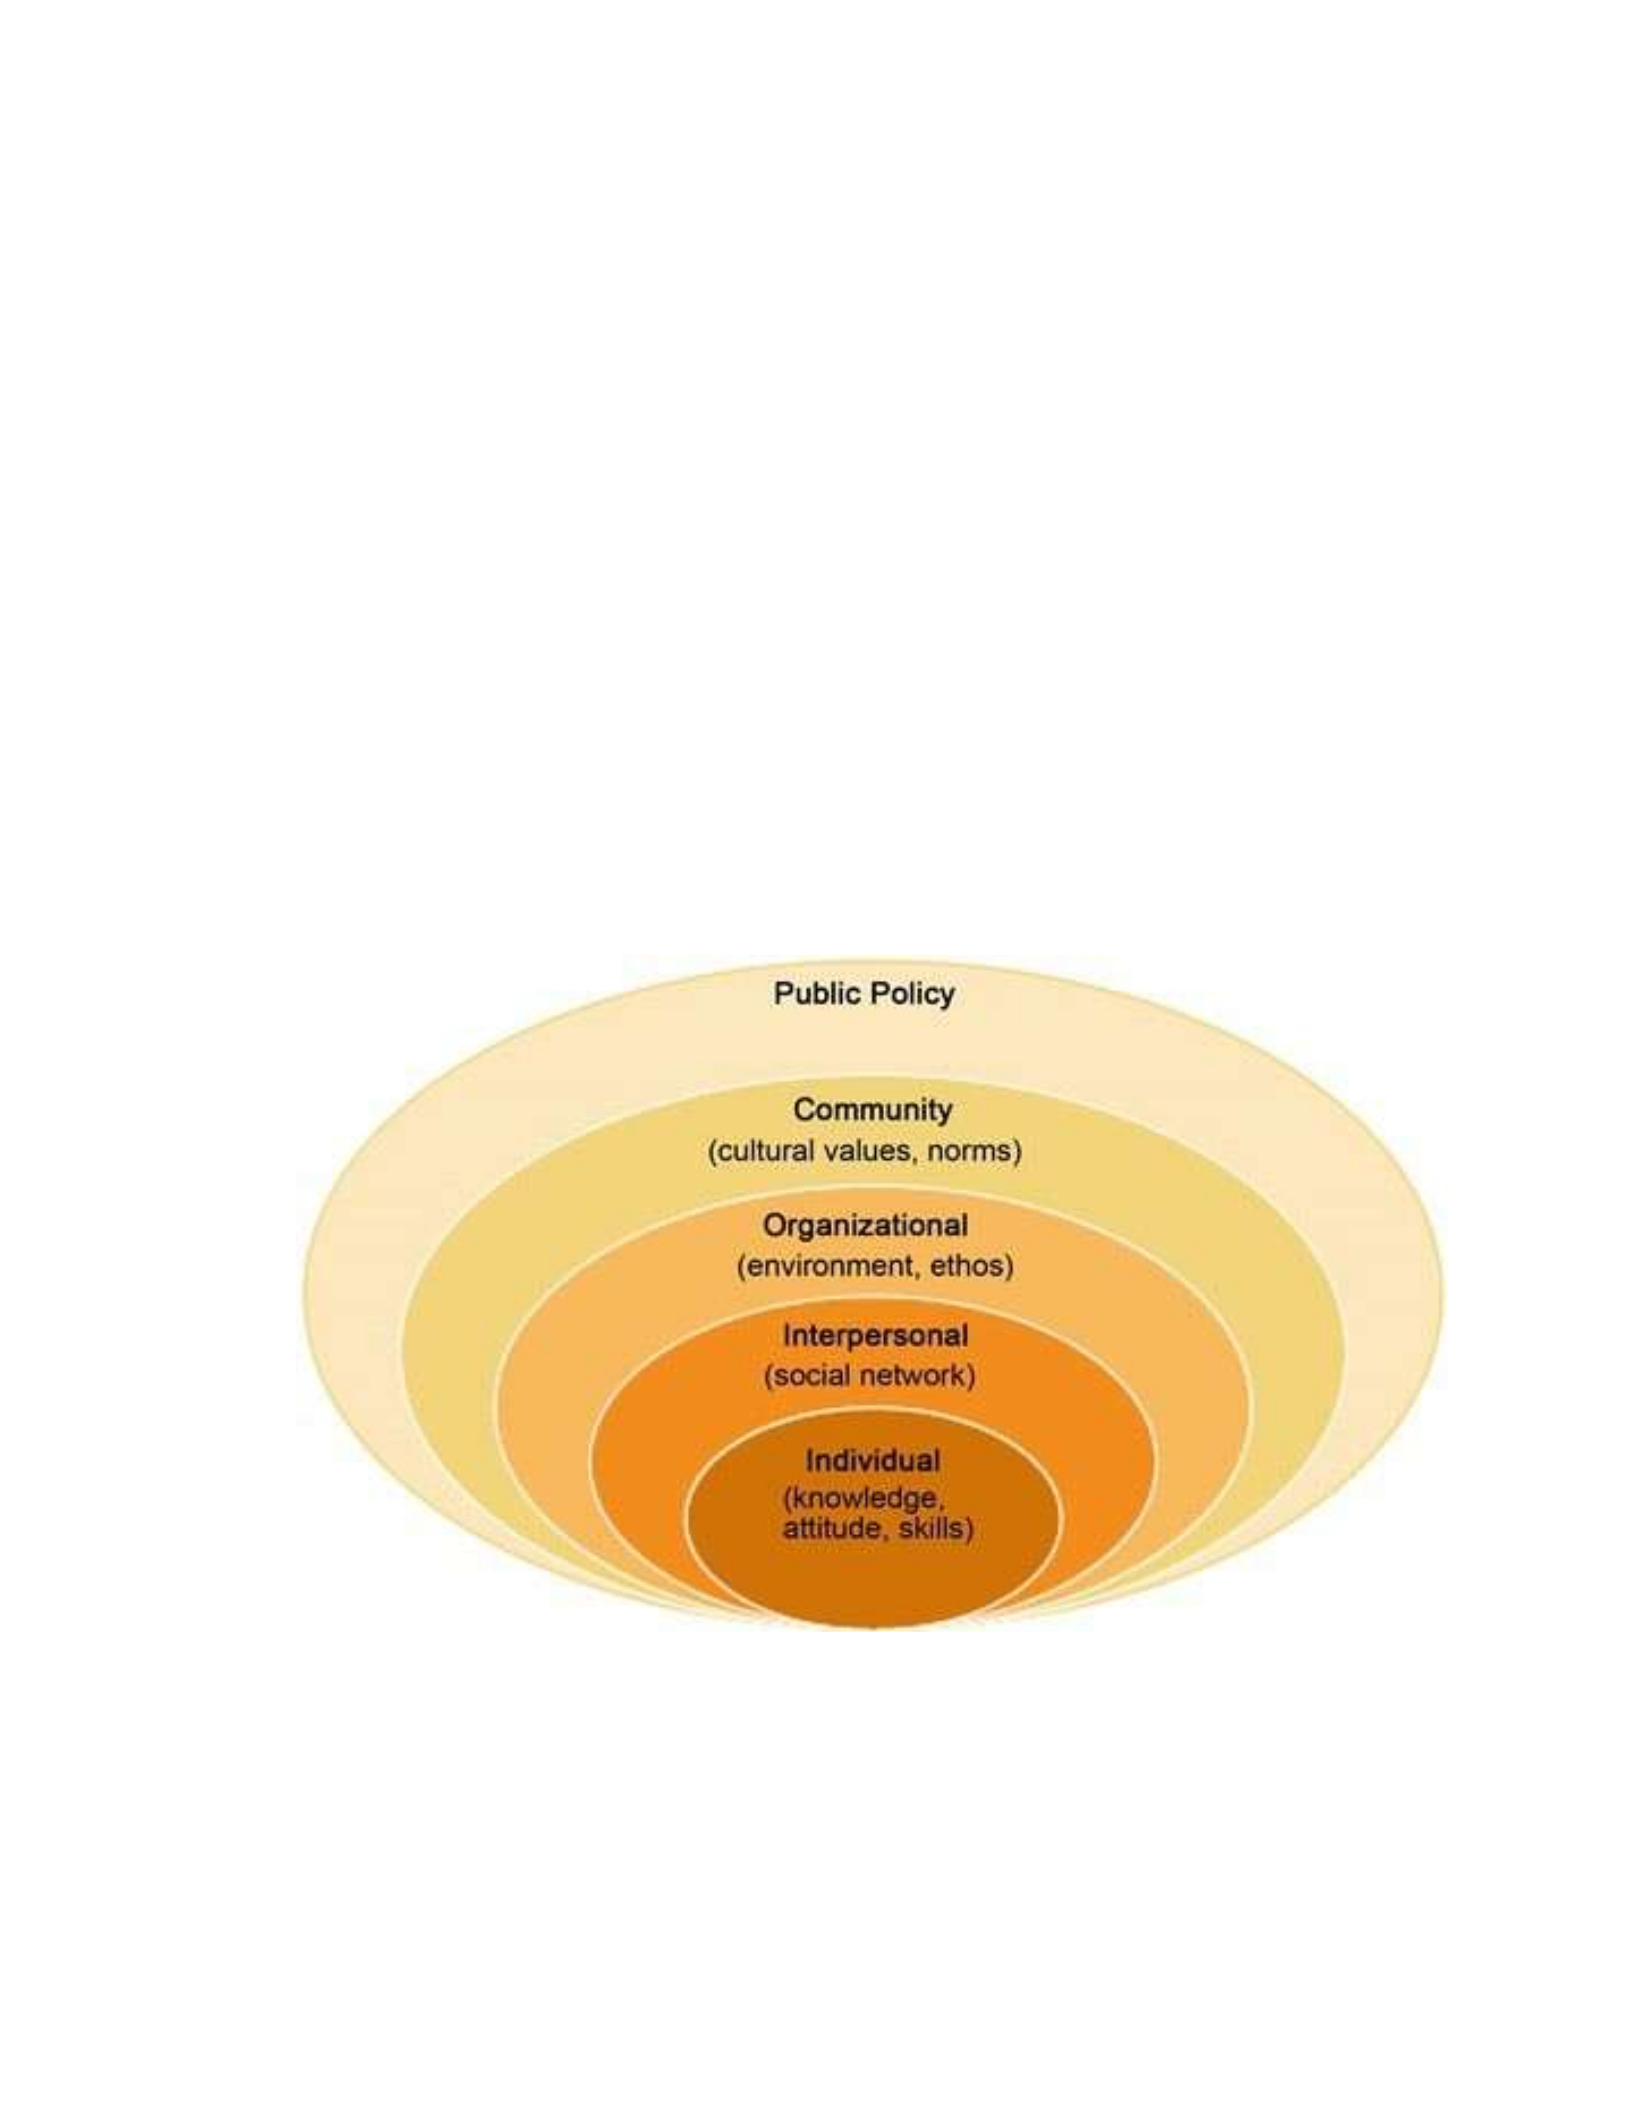
Figure 1 shows the factors in the SEM that can affect an individual.
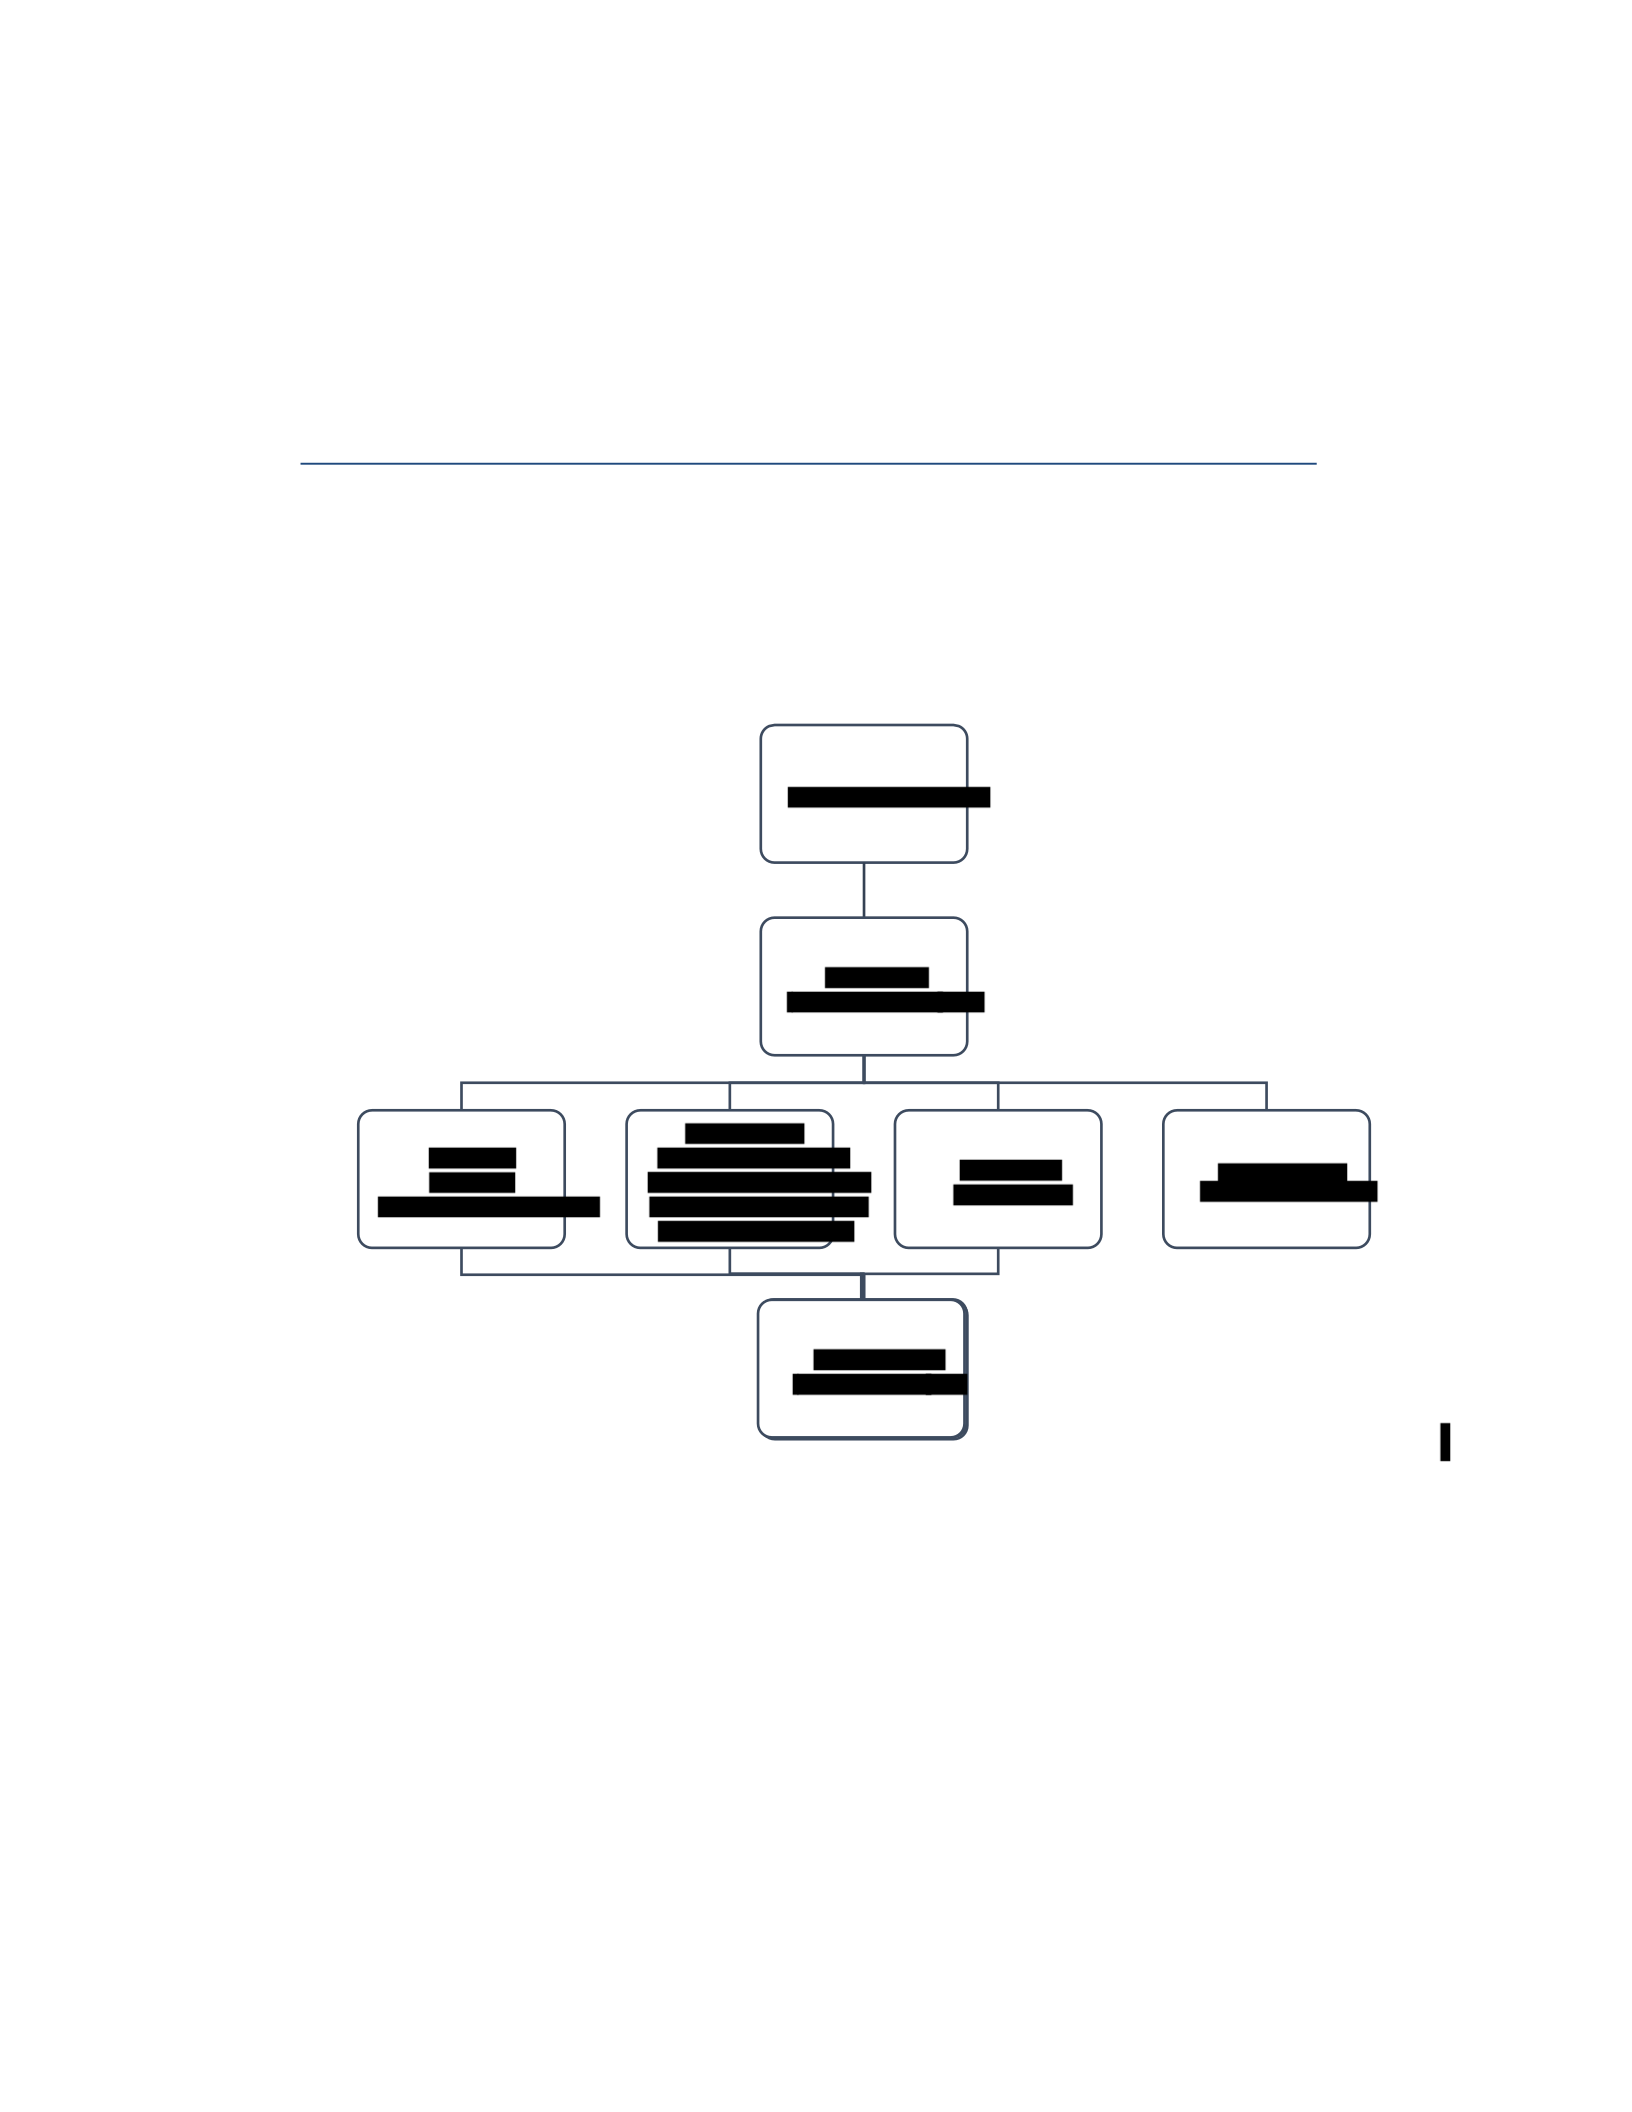
Figure 2 illustrates the SEM framework with respect to the independent and
dependent variables in this study: education, sex of head of household,
8
wealth index, area, location of water source, location of toilet facility, water
treatment type and number of families sharing a toilet facility. This
framework thus addresses all potential stakeholders who may be able to
undertake improvement strategies. I discuss the study variables with respect
to their
SEM categorization.
Figure 1
Theoretical Framework: The Socioecological Model
Note. The figure shows the factors in the socioecological model. Adapted
from Chapter 1: Models and Frameworks | Principles of Community
9
Engagement | ATSDR, by Agency for Toxic Substances and Diseases
Registry, 2015, Centers for Disease Control and Prevention
(https://www.atsdr.cdc.gov/communityengagement/pce_models.html). In the
public domain.
Figure 2
Study Variables
Individual
According to the SEM, the individual level focuses on biological and
personal history factors such as knowledge, attitudes, beliefs, and personality
(Centers for Disease Control and Prevention, n.d.-b; Scarneo et al., 2019).
Socio-Ecological Model
Risk Factors
)
(
Independent variables
Individual
Education
Sex of Head of Household
Interpersonal
Shared Toilet Facilities
Location of Water Source
Location of Toilet Facility
Water Treatment Type
Community
Wealth Index
Child mortality
(
Dependent variable
)
Organizational
Area (rural vs urban)

10
For this study, the associated variables included both education of head of
household and sex of head of household.
Interpersonal
The interpersonal level of the SEM model looks at the social impact of
friends and family on norms within social networks. This study included how
toilet facilities and water sources are used in Sierra Leone as they are
sometimes shared within communities.
Organizational
Organizational factors include living conditions such as the
environment, urban and rural living which could influence standards of
living and create adverse effects
(Mahmudiono et al., 2019).
Community
Community factors explore physical, cultural values, and norms, such
as schools, workplaces, and neighborhoods where social relationships happen
(Centers for Disease Control and Prevention, n.d.-b; Scarneo et al., 2019).
For this study, wealth index was grouped into community as many people
live according to their wealth status and what they can afford.

11
Public Policy
Although public policy was not a study variable, potential policy
updates that cater to study areas of weakness are discussed for future
improvements and social change implications.
Nature of the Study
To address the RQs in this quantitative study, I analyzed
secondary data from
UNICEF’s Multiple Indicator Cluster Survey (MICS), specifically the sixth
round
(MICS6) of the survey. The MICS6 data set provided valuable information
on various factors related to water source, treatment, and sanitation facilities
in Sierra Leone. The specific variables of interest included location of water
source, location of toilet facility, number of households using toilet, water
treatment type, area, wealth index, education, sex of head of household and
child mortality.
Literature Search Strategy
To find peer-reviewed journal articles for the study, I engaged in a
strategic literature search utilizing EBSCOhost and Google Scholar as the
primary web portals, which allowed access to several databases, including
Academic Search

12
Complete, Directory of Open Access
Journals, ScienceDirect, PubMed, MEDLINE, CINAHL Plus, Supplemental
Index, Business Source Complete, Complimentary Index, Education Source,
Gale Academic, One File, Journals@Ovid, and Science Citation Index
Expanded. The search for peer-reviewed articles was limited to the years
2013 to 2024, unless the subject necessitated historical context. Special
emphasis was placed on the past 5 years (2020– 2024). Articles were
retrieved using specific key search terms, entered both individually and in
conjunction with other search terms. These included socioecological model
(SEM), water, sanitation, hygiene (WASH) knowledge, education, gender,
gender-based violence, safe water, drinking water, quality water, low-
income, middle-income, low-or-middle income countries (LMICs), wealth
index, child mortality, Sierra Leone, water sources, and toilet facilities. The
literature search produced relevant peer-reviewed studies, which
I discuss in the literature review.
Literature Review Related to Key Variables and/or Concepts
The Socioecological Model
Bronfenbrenner initially introduced the original SEM in the 1970s as a
conceptual framework for understanding human development, before
transitioning to a theoretical framework (Kilanowski, 2017). The theory

13
focuses on how health is affected by the characteristics of the individual,
community, organizations, the environment, and public policy
(Bronfenbrenner, 1979; Kilanowski, 2017; Salihu et al., 2015; Scarneo et al.,
2019). The theory implies that behaviors both impact and can be impacted by
external factors. This includes people influencing their environment and
being influenced by it (Caperon et al., 2022; Salihu et al., 2015). The SEM
has been used for many aspects of public health such as community
engagement program interventions and mortality prevention (Caperon et al.,
2022; Scarneo et al., 2019). However, I was able to find only one article
using this framework related to child mortality in sub-Saharan Africa.
Gebremichael et al. (2021) conducted a community-based cross-
sectional study using the SEM. They looked at determinants of water source
use and the quality of
WASH perceptions among urban households in northwest Ethiopia.
Kousoulis and Goldie (2021) asserted that the SEM has been proposed
predominantly in rural settings as opposed to the urban setting Gebremichael
et al. looked at. The urban setting, however, could be more suited for the
SEM due to the limited and specific built environment and defined authority
of resources (Kousoulis & Goldie, 2021). Gebremichael et al. reviewed the

14
following variables: household drinking water sources, participant age,
educational status, source of income, monthly income, availability of
additional facilities, cleanness status, scarcity of water, and family size.
Using a logistic regression, they determined that factors such as toilet facility
availability, household member type, and sex of the head of the household
were not significantly associated with drinking water sources. Uses of water
were determined by demographic, socioeconomic, sanitation, and hygiene-
related factors. The connection between variables associated with
socioeconomic status and
WASH were further evaluated.
Water, Sanitation, and Hygiene
There are aspects of life that are considered essential to human
survival. Access to clean and safe drinking water, basic sanitation, and
hygiene are considered necessities
(Bayu et al., 2020; Chirgwin et al., 2021; Dery et al., 2019; Ohwo, 2019;
Ravindra et al., 2019; Sridhar et al., 2020). Across the globe, about
2,100,000,000 people do not have access to safe drinking water, and an
additional 2,000,000,000–4,000,000,000 lack access to basic sanitation,
resulting in the deaths of over half a million children annually (Berhe et al.,

15
2020; Daly et al., 2021; Dery et al., 2019; Manetu & Karanja, 2021; Murtaza
et al., 2021; Prüss-Ustün et al., 2019; Sridhar et al., 2020). These challenges
have led to large amounts of disease universally. M. H. Khan et al. (2021)
reported that over
2,000,000,000 people that year suffered from waterborne diseases. These
diseases led to illnesses and in some cases, death. Kaoje et al. (2019)
reiterated WHO’s estimate that 94% of the global diarrheal burden and 10%
of the burden of disease was attributed to inadequate WASH.
Diarrhea as a result of poor water, inadequate sanitation, and hygiene
is reported as the second highest cause of child mortality (Murtaza et al.,
2021). Although diarrheal diseases are seen in both developed and
developing countries, developing countries are impacted more (Manetu &
Karanja, 2021). Sultana et al. (2022) discussed a study in Nepal in which
researchers determined that the amount of water used can lead to diarrhea.
Not using enough water can be due to resource scarcity associated with
poverty or other hindering factors, which is discussed throughout my study.
Some subpopulations experience these adverse effects more than others like
those living in developing countries like Sierra Leone.

16
Dery et al. (2020) asserted that women, people from poor households,
and other marginalized groups who may not have access to certain services
are impacted more than others in terms of access to WASH. The inequality
ultimately impacts these individuals and their families at a socioecological
level. Other factors such as distance from water sources, open defecation
directives, and community participation during water construction (Aemiro
& Getachew, 2022). Therefore, Bisung and Dickin (2019) declared that
WASH interventions should be at individual and communal levels. These
inequalities are especially prevalent in developing countries and thus were
the focus of this study.
WASH in Developing Countries
According to Sesay et al. (2022), WASH challenges in LMICs are a
result of poor infrastructure services. These include how water is retrieved
for use, the quality of toilet facilities, and practices associated with poor
hygiene. A reason for this could be the measures taken to make WASH
services available in countries (Hosking et al., 2022).
These issues are seen in many aspects of life in LMIC countries (Hosking et
al., 2022; Kayser et al., 2019), leading to waterborne diarrheal diseases that
disproportionately impact developing countries and, ultimately, contribute to

17
high rates of mortality in adults and, more specifically, children (Girma et al.,
2021; Manetu & Karanja, 2021; PrüssUstün et al., 2019).
In recent years, researchers have explored sub-Saharan Africa,
Southeast Asia, and South Asia as the areas where water and sanitation
improvements are most needed (Swe et al., 2021). Studies have also shown
that LMICs have lower coverage in the water supply and sanitation sector
than higher-income countries. There are many factors indicative of WASH
practices and availability, some of which include local (rural or urban),
gender, and education. Swe et al. (2021) extracted water supply and
sanitation indicators from LMICs in South Asia, Southeast Asia, and sub-
Saharan Africa. This was a combination of 210 nationally representative
household surveys, which included 128 Demographic and Health Surveys
(DHS), 61 MICS, and 21 Malaria and AIDS Indicator Surveys from 1994 to
2016.
Swe et al (2021) determined that in urban areas, 80% of the countries
involved in the study could get over 90% coverage in access to basic
drinking water service, though sub-Saharan African countries saw slightly
lower numbers. Rural countries in Asia like Bangladesh, Bhutan, India, and
the Philippines would also get over 90% coverage in access to basic drinking

18
water services. This was an interesting insight as India, Bangladesh, and
other developing countries rely heavily on women for water collection
services (Bisung & Dickin, 2019). Countries in sub-Saharan Africa, Angola,
Central
African Republic, Madagascar, Liberia, Ghana, and Mozambique were
predicted to have less than 50% basic drinking water services regardless of
urban or rural locals (Swe et al., 2021).
To a similar effect, Sridhar et al. (2020) conducted a cross-sectional
study where they assessed the level of knowledge, behavior, and practices
towards WASH in Kaduna State, Nigeria with an emphasis on sanitation
practices. This was done with the use of a structured questionnaire and field
observation. Over 800 questionnaires were administered through the process.
The authors observed the presence of both human and animal feces around
the house (38.6%), in the house (25.1%), and near the water source (7.2%).
Traditional pit toilets (89.5%) were the most observed. Toilets were located
outside the compound 56% of the time. Hand wash facilities were located
inside the house 21.7% of the time or within walking distance 11.5% of the
time and next to the toilet (18.6%). Although these numbers were unique to
Kaduna State, Nigeria, they may be indicative of practices and behaviors in

19
other developing countries. Stakeholders may be able to use their findings to
improve WASH-related interventions in LMICs.
In another study, Girma et al. (2021) looked at data from Ethiopia’s
Mini DHS collected between 2000 and 2016 by ICF, Central Statistical
Agency, and ORC Macro. They determined that water service standard
improvements were made across all regions, although inequalities still
existed. The lack of WASH services was still stark. Only 6% of Ethiopian
households used a basic sanitation facility as of 2016. An additional 8% of
households had a handwashing facility with soap and water available on the
premises while 40% had no handwashing facility to speak of. One area in
Ethiopia did see improvements, however, was in open defecation processes.
In the 16 years covered by the study, open defecation decreased by 50%.
Many of the themes discussed were specific to sub-Saharan Africa.
WASH in Sub-Saharan Africa
Access to adequate sanitation is one of the biggest obstacles seen in
sub-Saharan Africa, which has the highest number of low-income countries
and where population health is not the best according to studies (Lanfer &
Reifegerste, 2021; Zerbo et al.,

20
2021). In this region of the world, 31% of people have access to basic
sanitation facilities (Bayu et al., 2020; Swe et al., 2021). Manetu and
Karanja (2021) noted that 23% of the sub-Saharan African population used
sanitation facilities where people can come in contact with fecal matter.
They also discussed outbreaks of water-related diseases as a result of poor
WASH services leading to 88% of diarrheal disease deaths in developing
countries.
Bayu et al (2020) conducted a two-step study using 2017 data sets
from the UNICEF/WHO Joint Monitoring Programme, analyzing 82
countries’ population access per wealth quintiles data to determine water and
sanitation access equality in developing countries. Their analysis disclosed
the inequalities of water and sanitation access present in many sub-Saharan
African countries but not necessarily all. In terms of water inequality,
countries with low living standards generally had higher levels of inequality
for basic services. Two countries that had opposing WASH situations were
Benin and Zambia. Benin, located in West Africa, had high levels of
sanitation inequalities and low levels of inequality in water access whereas
Zambia, located in southern Africa, saw low levels of sanitation inequality
and high levels of water access inequality. The authors could not say why

21
these countries had differing experiences but inferred that individual country
priorities could play a key role in the results seen.
Different studies have shown several factors to impact WASH
services including gender, educational attainment, age, and income of the
head of household (Gebremichael et al., 2021). Researchers have also
examined knowledge, attitudes, and practices to determine why vast gaps
exist in parts of the world (Calderón-Villarreal et al., 2022). Other
byproducts of poor WASH access were malnutrition and food insecurity,
research showed (van Cooten et al., 2018). Specifically, regions of both
South Asia and subSaharan Africa have been adversely impacted (Chirgwin
et al., 2021). As such, leaders of many countries have created initiatives to
achieve universal access to WASH services by 2030 (Bisung & Dickin,
2019). In sub-Saharan Africa, specifically rural areas, where most of the
population resides, basic water and sanitation coverage was limited (Bisung
& Dickin, 2019; Sultana et al., 2022). Ngasala et al. (2020) discussed how
areas like northeastern Tanzania have limited access to clean water while
Tumwebaze et al. (2022) discussed slightly better conditions for urban
populations. The factors that influence WASH in sub-Saharan Africa is a
continuous theme seen in the present study.

22
WASH and Rural/Urban Differences
One of the largest gaps seen with WASH was that between rural and
urban communities. Chaudhuri and Roy (2017) asserted that the inequalities
between rural and urban households created severe challenges in developing
countries. According to
Rheingans et al. (2013), in almost every developing country urban
households were in a higher national wealth quintile than rural households.
In sub-Saharan Africa, the rural/urban WASH divide is even greater than
expected.
Across sub-Saharan Africa, urban communities had more access
to drinking
WASH (Abrams et al., 2021; Ravindra et al., 2019; Ohwo, 2019; Zerbo et al.,
2021). There were many reasons for this. Zerbo et al. (2021) discussed an
increasing urban population due to climate change, conflict, and poverty to
name a few. This was something that has occurred in sub-Saharan Africa
over the last 50 years (Abrams et al., 2021). Socioeconomic status was a key
factor in WASH differences in and between rural and urban areas, with even
the poorest urban areas having difficulties with WASH (Abrams et al., 2021;

23
Zerbo et al., 2021). Aspects of everyday life in sub-Saharan Africa became
difficult in rural areas as travel time is increased, especially in countries like
Nigeria (Ohwo, 2019). Many people in rural communities in Nigeria lived
without safe WASH facilities (Sridhar et al., 2020). Ohwo (2019) conducted
a study in Nigeria where he looked at inequalities in urban and rural WASH
availability with a descriptive design. His most critical findings were the use
of surface water in rural areas (15%) versus urban areas (2%); open
defecation in rural areas (32%), 8% in urban areas, and 40% improved
sanitation in urban regions versus 23% in rural populations. These findings
aligned with similar studies conducted on WASH and rural/ urban
differences.
Ravindra et al. (2019) conducted a community-based cross-sectional in
Chandigarh, India to evaluate water and sanitation facilities as well as
practices of the people living in rural areas of Chandigarh. Even as one of the
world's most known developing countries, 66% of the population did not
have access to clean water and used contaminated water as the primary
source. Clear rural/urban differences were seen within the region. Rural
populations showed clear discrepancies in treated tap water, improved water
sources, at-home water sources and toilet facilities. Similar studies were

24
conducted by Aleixo et al. (2019) in Brazil and Tumwebaze et al. (2022) in
Sierra Leone. Studies done on WASH in rural and urban settings tended to
focus on specific aspects of the services: water source, safe drinking water,
and toilet facilities.
Sources of Water. In rural households, the main sources of drinking
water were unprotected wells, unprotected springs, surface water, and sachet
water (Kaoje et al., 2019). The authors asserted that almost all households do
not treat these sources of water prior to use. Sources of water were
characterized as improved or unimproved
(Gebremichael et al., 2021). Examples of improved sources of drinking water
given by Gebremichael et al. (2021) included piped supplies such as tap
water, and non-piped supplies such as boreholes, protected wells and springs,
rainwater, and packaged water; unimproved water sources on other hand
include water collected from unprotected dug wells, unprotected springs, and
surface water. The sources of surface water mentioned were more susceptible
to potentially toxic elements and contamination than groundwater sources
(M. H. Khan et al., 2021). Gebremichael et al. (2021) discussed the various
reasons for using unimproved water sources which included: income,
distance from a clean water source, availability of other sources, the amount

25
of water needed, water quality, and the time it took to get water to name a
few. Daly et al. (2021) reviewed several articles that stated that urban
households tend to use multiple water sources and a greater number of water
sources compared to rural households, although results were inconclusive
from one country to the next.
Safe Drinking Water. Clean water is an essential part of life
(Gebremichael et al., 2021). Bain et al. (2021), Gebremichael et al. (2021),
and Kaoje et al. (2019) estimated over 1,000,000,000 people drank water
from contaminated sources. Unsafe water was the cause of water-borne
illnesses such as diarrhea, especially in rural households which were a major
public health concern (Gebremichael et al., 2021; Kaoje et al., 2019).
Gebremichael et al. (2021) discussed the causes of drinking water
contamination: floods, animal or human feces, and other forms of waste to
name a few. Data on water quality was often lacking for the majority of the
population in many LMICs. Working with UNICEF and aided by MICS, new
water quality modules were created and offered as part of MICS surveys
moving forward, allowing the opportunity to look at risk factors for fecal
contamination of drinking water in LMICs (Bain et al., 2021). With

26
improvements to drinking water quality, incidents of diarrhea can be reduced
by at least 4% (Tessema & Alemu, 2021).
Access to Toilet Facilities. Access to toilet facilities in sub-Saharan
Africa was a major source of public health angst. Kaoje et al. (2019) noted
that lack of sanitation facilities was a public health risk. This was prominent
in both rural and urban populations in sub-Saharan Africa. Gebremichael et
al. (2021) asserted that 45% of the rural population had access to improved
sanitation services, leading to people defecating in open fields, in rivers, or
near areas where children play, and food was prepared. Obeng et al. (2019)
reported over half the urban population in sub-Saharan Africa used pit
latrines.
The state of pit latrines allowed a breeding ground for diseases and unsafe
environments (Kipkoech et al., 2023; Obeng et al., 2019; Osumanu et al.,
2019). Diarrheal diseases spread when inadequate water is used for personal
hygiene (Sultana et al., 2022). Kaoje et al. (2019) noted that in Nigeria, over
60% of rural households used non-improved facilities such as flush/pour
flush not to sewer/septic tank/pit latrine, pit latrine without slab/open pit,
bucket, hanging toilet/hanging latrine, and no facility/bush/field as sanitation
facilities. Another sub-Saharan African country, Ghana’s population reported

27
that 85.7% of the population did not have access to decent toilet facilities in
2017 and ranked highly globally among countries with poor human waste
management practices (Cobbinah et al., 2020). Obeng et al. (2019) declared
pit latrines as the most popular sanitation technique in Ghana, opening the
population up to disease and potential acts of violence.
Because of this, Cobbinah et al. (2020) conducted a study to analyze
the social, economic, institutional, and cultural factors preventing the
acquisition of toilets in urban Ghana. They determined wealth to be a
contributing factor in the affordability and maintenance of a toilet facility.
Kipkoech et al. (2023) revealed that 79% of the respondent households in
Ghana could access the household toilet facilities and another 14% had
access to other toilet facilities; the remainder of households however
practiced open defecation. Similar to adult toilet facility use, children's
defecation practices showed 72% could access household toilet facilities,
16% had access to other toilet facilities and open defecation was reported at
11% (Kipkoech et al., 2023). Aemiro and Getachew’s (2022) study in
Northeast Ethiopia reflected, that 39.4% of respondents declared their village
declared open defecation, and the other 60% stated their village had not
declared open defecation. Several factors contributed to sources of water,

28
access to safe drinking water, and toilet facilities, one of which was
household income/ wealth.
WASH and Wealth Index
There were many factors associated with adequate access to WASH
services. Rheingans et al. (2013) discussed the history of wealth as it related
to having access to sufficient WASH services, offering the sentiment that
poorer households were more likely to have poor sanitation, which would
then create the association even in the reverse. One of those factors that has
been studied in recent years was wealth index. Swe et al. (2021) researched
how leaders of LMICs could improve the coverage of WASH, specifically in
the sanitation sector as individuals in the lower half of the wealth index were
more likely to participate in open defecation, and 60% less likely to have
access to improved sanitation facilities. This assessment was further
confirmed through the study conducted by Gebremichael et al. Gebremichael
et al. (2021) conducted a cross-sectional study on determinants of WASH
perceptions in urban Ethiopia. One of their biggest takeaways was a
significant association between monthly income and source of water. Income
had a key role in many aspects of life, one of the primary variables being
education.

29
WASH and Education
Another variable considered when looking at WASH services was
educational attainment. Simply put, the success of WASH services depended
on not only the availability of services, but people using them, correctly
(Berhe et al., 2020). This was why education was a pertinent aspect to the
success of WASH use and any potential interventions. Sridhar et al. (2020)
discussed the importance of knowledge, attitudes, and practices as they relate
to the sustainable and effective implementation of WASH programs. They
mentioned how poor WASH knowledge can and has led to unhygienic
practices and poor attitudes leading to contamination and the spread of
diseases, specifically those that were waterborne.
One of the determinants discovered by Gebremichael et al. (2021)
during their study in Ethiopia was that participation in education and
awareness activities regarding WASH played a large role in community
health. As a part of Tumwebaze et al. (2022) study, they identified
education’s impact on WASH. Those with no formal education were more
likely to lack sanitation facilities (Tumwebaze et al., 2022). Pouramin et al.
(2020) further asserted that education was pivotal in improving WASH and
had been named as an intervention in some countries to accomplish goals.

30
Similar studies were conducted by Sridhar et al. (2020) and Swe et al.
(2021), both determined that education, specifically, WASH education was
important for good WASH practices and behaviors while coinciding with
country-specific economic factors. While many of these variables showed a
great deal of intersectionality, there were none more than gender factors on
WASH accessibility.
WASH and Gender Factors
One of the greatest discrepancies in terms of WASH was gender. This
was due to gender-affirming norms perpetuated in developing countries,
which were often referred to as imperative for women's empowerment and
gender equality (Dicken et al., 2021).
Previous studies acknowledged the role WASH had in the lives of women
and girls.
According to Bisung and Dickin (2019), in developing countries, specifically
in subSaharan Africa, where women and girls were primarily responsible for
water collection, there were added ingrained biological discriminations
(Gebremichael et al., 2021; Kayser et al., 2019). Gebremichael et al. (2021)
stated that 64% of women, 24% of men, 8% of girls and 4% of boys were
tasked with water collection where it was not easily accessible.

31
This severely put women and girls at a disadvantage as it related to other
factors.
Of the traditional gender assignments, women and girls faced greater
consequences as a result of WASH services. WASH services and gender
show the intersectionality of other factors such as educational attainment and
income, specifically in rural areas. Bisung and Dickin, (2019) discussed the
biological aspects that contributed to WASH inequalities. For women and
young girls, there is an added need for access to WASH. One of those factors
was menstrual hygiene. Every month, women and girls required access to
menstrual materials to manage bleeding, private facilities to change
menstrual materials, bathing facilities, clean water, toilet paper and/or soap
and water to wash and dry themselves, and soak, wash, dry and/or dispose of
used materials (Calderón-Villarreal et al., 2022; Pouramin et al., 2020).
These results suggested that when a woman was the household head and had
greater decision-making power with respect to the sources used, there was a
greater tendency to use sources of higher quality, such as the water supply
and sanitation and probably bottled water (Aleixo et al., 2019).
Bisung and Dickin,(2019)) asserted that young girls education was
impacted by limited WASH access as they sometimes had to skip school to

32
collect water for their families or to simply avoid having to deal with poor
sanitation, further increasing the economic gender burden and leaving
themselves open to gender-based violence (GBV) (Calderón-Villarreal et al.,
2022; Habtegiorgis et al., 2021; Kayser et al., 2019; Nunbogu et al., 2023).
Nunbogu et al. (2023) discussed GBV and its association with WASH as
participants of their study shared their personal experiences of gender
inequalities or those of people in their neighborhoods. Many acts of violence
took place at home, the water source or latrine. Studies by Dicken et al.
(2021), Kayser et al. (2019) and
Pouramin et al. (2020) confirmed these claims as each study found similar
outcomes. Pouramin et al., 2020 looked at studies focused specifically on
women and girls, discovering that lack of resources contributed to poor
sanitation and hygiene practices. This was due to a lack of privacy and
security where women felt unsafe, predominately at night, further
contributing to the disempowered women felt at the individual, household,
and societal levels (Dicken et al., 2021; Pouramin et al., 2020). Women were
adversely impacted by the lack of WASH service; however, no population
was more affected than children.

33
WASH and Child Mortality
Child mortality is an important indicator used to determine a country's
socioeconomic standing, as such it is still an issue and cause for concern in
many developing countries (Lu et al., 2019). Previous studies have looked at
the link between child mortality and WASH from various perspectives (Liu,
2021). According to Sridhar et al. (2020) children were most impacted by
lack of access to WASH. This lead to diarrhea-influenced mortality globally,
a leading cause of mortality in this population (Bizzego et al., 2021;
Fagbamigbe et al., 2021; Girma et al., 2021; Reiner et al., 2020). In 2016
alone, WASH access contributed to 5.3% of under-5 deaths and 60% of total
diarrheal deaths (Daly et al., 2021; Fagbamigbe et al., 2021; Prüss-Ustün et
al., 2019; Ugboko et al., 2020; Wolf et al., 2018). Many studies have been
conducted to assess the validity of these statements. Mebrahtom et al. (2022)
looked at causes of child mortality in Ethiopia. They discovered appropriate
WASH access impacted child mortality via diarrheal diseases. Education,
specifically mother’s education showed great significance. Fagbamigbe et al.
(2021) described similar risk factors, iterating that this must be looked at
through a socioecological lens.

34
Murtaza et al. (2021) looked at water and sanitation risk exposure,
specifically as it related to diarrheal disease in children under-5 in Pakistan.
The authors determined that 55% of children in urban areas had access to
pipe-borne water compared to 13.5% of children in rural areas. WASH
improvements and interventions could reduce diarrheal disease and
ultimately reduce incidents of child mortality (Wolf et al., 2018). Lu et al.
(2019) also suggested that infant mortality rates could be significantly
reduced by increasing access to improved water, sanitation, and healthcare
facilities.
Another cause for concern with inadequate WASH services that has
led to child mortality was the impact of water stress on nutrition (Liu, 2021).
Water used for cooking and drinking can adversely impact a child's health
leading to diarrhea or other illnesses. Surprisingly, Liu (2021) discovered a
very weak and negative association between the level of water stress and
child mortality in developing countries. This is not consistent with other
studies discussed. However, the authors believed this weak correlation may
have existed because water is not being used while cooking. Unfortunately,
many developing countries were unable to provide a level of stability to their

35
populations (Lu et al., 2019). In many cases, this led to high rates of
mortality for vulnerable populations, specifically old and young populations.
Child Mortality in Developing Countries
In developing countries, WASH inadequacies were linked with high
rates of child mortality yearly due to diarrheal diseases (Jacobs et al., 2023;
Reiner et al., 2020; Sridhar et al., 2020). While under-5 mortality had
decreased, was still high in developing countries, specifically in Africa
(Ingutia et al., 2020; Van Malderen et al., 2019). Child mortality was a global
health issue and an indicator of child health (Ingutia et al., 2020; Van
Malderen et al., 2019). Water-related diseases were responsible for an
estimated 21% of the global disease burden, killing almost 1,000,000 people
yearly, 33% of those people being children under the age of five (Bizzego et
al., 2021; Dey et al., 2019). Children in LMICs were 10 times more likely to
be affected than children in high-income countries (Fagbamigbe et al., 2021;
Waddington et al., 2023). Although child mortality had decreased 60% over 3
decades, child mortality remained high in LMICs, specifically those located
in sub-Saharan Africa (Ingutia et al., 2020; Jacobs et al., 2023; Jensen et al.,
2023; Salzberg et al., 2019). Those who lacked access to WASH were

36
typically the poorest and most marginalized, which added importance to the
cost and the efforts of reaching universal coverage (Wolf et al., 2018).
Waddington et al. (2023) conducted a systematic review and meta-
analysis reviewing WASH-related incidents of child mortality. They
determined respiratory and diarrheal infections primarily associated with
WASH were linked to death. Studies have shown there were emerging
factors related to child mortality rates in LMICs, which included sex and
wealth status, with absolute disparities in mortality declining between the
poorest and richest households but with persistent relative differences
(Mejía-Guevara et al., 2019). These factors were discussed with respect to
child mortality in LMICs.
African Status of Under-5 Mortality
In sub-Saharan Africa, child mortality was an immense public health
issue (Ekholuenetale et al., 2020). Between 2017 and 2018, 5,300,000
children died; about half of those deaths happened in sub-Saharan Africa
(Beatriz et al., 2018; Midtgaard Eriksen et al., 2021; Tesema et al., 2021).
Ekholuenetale et al. (2020) also stated that household structure plays a
significant role in child mortality in sub-Saharan Africa. From a
socioecological perspective, child mortality varied across individual,

37
communal, and socioeconomic factors (Ingutia et al., 2020; Van Malderen et
al., 2019; Yaya et al., 2021).
One of the leading causes of death in LMICs was diarrhea related to
poor water and lack of sanitation and hygiene (Mebrahtom et al., 2022). Sub-
Saharan Africa had a high rate of diarrheal disease with increasing rates of
malnutrition as well (Ingutia et al., 2020; Reiner et al., 2020). Nwokoro et al.
(2020) conducted a study in a rural community in Southeast Nigeria
determining that children younger than five were 59% more likely to get a
diarrheal disease compared to the rest of the community. This was however
found not to be statistically significant. While these results were surprising,
the authors did noted that lack of significance could have been due to the
number of children within that community under the age of five not being
large enough. Jacobs et al. (2023) looked at how Zambia decreased its under-
5 mortality rates in a 20-year period without large changes in socioeconomic
discrepancies. In fact, wealth group and education level changes did not
occur at the same time. They determined that government action helped to
decrease inequalities and ultimately, child mortality.

38
Child Mortality in Rural/Urban Differences in Sub-Saharan Africa
In sub-Saharan Africa, a rural/urban divide has been seen in terms of
child mortality. Many attributed this divide to area poverty differences
Ekholuenetale et al.,
2020). Beatriz et al. (2018) claimed that children living in urban areas were
more than 20% less likely to die before the age of five than children living in
rural areas. They added that the disparity continued to increase with the
expansion of the urban population. Midtgaard Eriksen et al. (2021) reviewed
several studies, all affirming the connectedness of child mortality to wealth
and area, noting that children in rural areas were 1.5 times more likely to die.
This was partly because of children in rural areas' socioeconomic standing;
their parents are under-educated leading to a lack of access to health services,
unsafe water sources or even basic sanitation (Ingutia et al., 2020).
Conversely, Yaya et al. (2021) looked at the rural/urban gap in 35 sub-
Saharan countries using DHS data. Their research had conflicting results. Of
the 35 countries, 17 showed no statistical association in the rural/ urban gap;
16 showed a statistical link in rural area inequality and the remaining showed
a statistical link in favor of urban area inequality. Both socioeconomic and
regional differences played a role in under-5 mortality rates as other factors

39
could have contributed to differences in disparity (Mejía-Guevara et al.,
2019). While the results in the latter study were inconclusive, they reflected
the importance of looking at child mortality through the lens of several
variables.
Wealth Index and Child Mortality in Sub-Saharan Africa
Sub-Saharan Africa was the only region known to have rising child
malnutrition (Ingutia et al., 2020). According to Ingutia et al. (2020), child
malnutrition was linked to growing up in poor families that lacked access to
adequate nutritious food, leading to a large percentage of under-5 child
deaths recorded. In conjunction with education, job type, area and wealth
were key indicators of socioeconomic status and ultimately child mortality
regardless of whether a country is considered low-, middle-, or high-income
(Allwell-Brown et al., 2021; Bizzego et al., 2021; Midtgaard Eriksen et al.,
2021).
Children from poorer families tended to face disease and more
dangerous situations related to home safety (Bizzego et al., 2021). Studies
showed a link between poverty and child mortality; more specifically,
children from poorer families were 2.5 times more likely to experience high
rates of mortality (Midtgaard Eriksen et al., 2021; Yaya et al., 2021). The

40
association further detailed that those who have better financial opportunities
were more likely to live in or move to urban areas, putting their families in a
better situation to receive health care if needed. Fagbamigbe et al. (2021),
conducted a secondary data analysis using DHS from 57 LMICs collected
between 2010 and 2019. They discovered that wealth was the most
meaningful factor for education and risks of diarrheal diseases as poorer
households were more impacted and less likely to receive health care
services with an associated cost. These findings were consistent with others
done on socioeconomic factors in LMICs. For women and girls, the results of
the many studies mentioned above was consistent with disparities seen
globally.
Gender and Child Mortality in Sub-Saharan Africa
One of the biggest indicators of child mortality in sub-Saharan Africa
was gender of head of household, specifically as it related to women.
Socioeconomic status as it related to women and their households was an
important determinant of child mortality
(Asif et al., 2022). Bizzego et al. (2021) reported that socioeconomic status
improvements for mothers who were head of household was associated with
decreased child mortality. For women, this was also tied to their educational

41
attainment (Yaya et al., 2021). Women living in rural settings have a steeper
hill to climb. Ingutia et al. (2020) claimed that the well-being of children was
tied to their mothers, specifically in rural communities.
Van Malderen et al. (2019) looked at factors influencing under-5
mortality in subSaharan Africa using the SEM. They saw a link between
mother’s education, sex of the child, household wealth, and child mortality.
Countries such as Cameroon and Niger saw a decline in under-5 mortality
over 20 years because of government policies regarding women’s education,
improving awareness and inevitably, child health and hygiene. Other studies
showed a link between diarrhea in children and mother’s education in several
developing countries (Fagbamigbe et al., 2021). Ekholuenetale et al. (2020)
and Mensch et al., (2019) had similar findings determining that mother's
education was more important than father’s income in child health outcomes
in most developing countries, creating women’s empowerment and
improving the use of health services. With Sierra Leone’s current child
mortality rates, taking all these factors into consideration was critical in
reducing mortality rates.

42
Adult Education and Child Mortality in Sub-Saharan Africa
One of the variables that coincided with gender in terms of child
mortality outcomes was education. Many studies have discussed the
relationship between education and child mortality, specifically as it related
to mothers (Asif et al., 2022; Ingutia et al., 2020; Mensch et al., 2019).
Bizzego et al. (2021) asserted children of uneducated mothers were 2.6
times more likely to die before five compared to children of mothers with a
high school education or higher. Bhusal and Khanal’s (2022) literature
search comparably revealed that mother’s education was the most significant
factor associated with under-5 mortality for several sub-Saharan Africa
countries. Similarly, Anyamele et al. (2020) ascertained that in many
Nigerian states, a strong association was present between educational
attainment and decreased infant mortality in rural over urban areas. Even in
terms of illness, Allwell-Brown et al. (2021) declared most sick children
under the age of 5 years had mothers who were not as educated, specifically
in LMICs.
A study conducted by Balaj et al. (2021) determined that increased
parental education was associated with a decrease in under-5 mortality. More
specifically, mothers education was a stronger predictor. The expectation

43
based on the study results was that mothers who were well educated knew
how to take care of themselves and their children during and after pregnancy
compared to those who were not as educated (Asif et al., 2022). In similar
fashion, a study conducted by Fagbamigbe et al. (2021) determined that
diarrhea, which can lead to death, was more prevalent among children born
to illiterate mothers. Sub-Saharan African countries such as Ghana, Nigeria,
Cameroon and Niger showed a link between education and government
policies on women’s education and a decline in under-5 mortality rates (Van
Malderen et al., 2019).
Child Mortality in Sierra Leone
In general, Sierra Leone has one of the highest overall mortality rates
in the world. Sierra Leone’s civil war destroyed a lot of the country’s health
infrastructure, creating long-lasting effects on its health system (Liwin &
Houle, 2019). Sesay et al. (2022) argued that 20% of all deaths in Sierra
Leone were attributed to WASH-related diseases. This included but was not
limited to diarrheal diseases. Tumwebaze et al. (2022) furthered this claim
with their own, stating that only 11% of the population had non-
contaminated water sources and 14% had access to safely managed
sanitation. In Sierra Leone, 95% of improved water sources were reportedly

44
contaminated due to limited WASH knowledge; 68% of the population used
unsafe hygiene practices; 58% used unimproved water sources; and 19%
practiced open defecation (Sesay et al., 2022).
Sierra Leone also had one of the highest child mortality rates
in the world
(Carshon-Marsh et al., 2022; Koroma et al., 2022; Liwin & Houle, 2019; Naz
et al., 2020; Tagoe et al., 2020). Turienzo et al., (2023) argued that child
mortality was closely linked with maternal mortality, education, and
socioeconomic status. Liwin and Houle (2019) conducted a study using 2013
DHS data from Sierra Leone to determine mortality frequency. They
determined that higher incidents of child mortality occurred in rural areas.
Surprisingly, mortality risk was higher for children born into the richest
families, with a hazard ratio 66% higher than children from families with
lower economic status (Liwin & Houle, 2019). Another surprising discovery
was that mother’s education did not affect the risk of mortality (Liwin &
Houle, 2019). Naz et al. (2020) discussed the decades-long plight infectious
diseases had on child mortality and how factors such as parent's occupation,
mother's education, population density, gender needs of children, nutritional
insufficiency, and poor maternal health care were risk factors of child

45
mortality in the region. The study they conducted included a bivariate
analysis which showed that under-5 mortality was lower for educated
mothers.
Tagoe et al. (2020) also conducted a study where they looked at data
from 2008 and 2013 on socioeconomic and demographic determinants of
under-5 mortality in Sierra Leone. Of the variables that were be addressed,
the ones considered important risk factors included: maternal education, type
of toilet facility used by household, and source of drinking water. Research in
Sierra Leone was not prominent. In fact, Liwin and Houle (2019) and Tagoe
et al. (2020) asserted that a gap in under-5 mortality research was present.
The goal of this study was to fill this gap with the most current data
available.
Gaps and Emerging Research Directions
There were a few gaps in the literature that still exist today. One of
which was the rural/urban divide in WASH. A lot of focus on WASH tends to
skew towards rural areas. Hague and Freeman (2021) reported limited
information on WASH services in urban areas of LMICs. This continued gap
had and will continue to limit interventions needed in urban areas as their
population continues to grow. Another gap was the way mortality were

46
reported, specifically in Sierra Leone. This gap inadvertently skewed the
information reported and as a result, potential problem-solving interventions.
Methodological Critique of Sources
A key indicator that emerged from the literature sources was the
interconnectedness of societal factors such as mother's education, wealth
index, and area on the impact of having WASH access as well as child
mortality. Many of these variables were discussed in alignment with others
and not necessarily individually, making it difficult to know if any of them
individually had an impact or only when combined with another variable.
This was further assessed in this study as the focus shifted to the used
research and data collection designs.
Definitions
Child mortality: Death in the 1st years of life; it is a health indicator of
social and material conditions (Chivardi et al., 2023).
Education: “The deliberate, systematic, and sustained effort to
transmit, provoke or acquire knowledge, values, attitudes, skills” (Chazan,
2021, pp. 13–21).

47
Head of household: The main decision-maker who is responsible for
finances and welfare of the household (Economic and Social Commission for
Western Asia, n.d.).
Hygiene: Behaviors that can improve cleanliness and lead to good
health (Centers for Disease Control and Prevention, n.d.-b).
Multiple Indicator Cluster Survey, Sixth Round (MICS6): An
international household survey program developed and supported by
UNICEF. It has become the largest source of statistically sound and
internationally comparable data on children and women worldwide
(UNICEF, n.d.-a; WHO, n.d.).
Rural residence: An area that is not designated a core-based statistical area
per the
Office of Management and Budget (OMB) (X. Chen et al., 2018).
Safe water: Water that causes no major health risk over a lifetime of
consumption
(Murtaza et al., 2021; Sridhar et al., 2020).
Sanitation: Access to facilities for the safe disposal of human waste
and the ability to maintain hygienic conditions (Centers for Disease Control
and Prevention, n.d.a).

48
Toilet facility: A fixture maintained for defecation and urination
(Occupational
Safety and Health Administration, n.d.).
Urban residence: An urbanized area with a population of at least
50,000; it is classified as a core-based statistical area per OMB (X. Chen et
al., 2018).
Wealth index: A complete measure of a household's cumulative living
standard
(The Demographic and Health Surveys Program, n.d.).
Assumptions
Research assumptions are things we accept as plausible or true. This
study had several. Using UNICEF’s MICS6 data, the assumption was made
that all participants were not coerced and answered all questionnaires
truthfully and without assistance from interviewees or outside sources.
Another assumption that was made was that participants were chosen via
random sampling and that all instrumentation used was determined prior to
the start of surveys being administered. It was also assumed that the
interviewees remained unbiased, distant, and independent of what was being
researched (Chancellor’s Doctoral Incentive Program, n.d.). I further
assumed that the participant’s information was obtained because they

49
understood the questions being asked to them. The assumption that
participants were representative of the intended population was also inferred.
These assumptions allowed for the ability to test the association between
WASH interventions and child mortality with no preconceived notions.
Scope and Delimitations
This was a cross-sectional study that explored the association between
aspects of
WASH and child mortality in Sierra Leone using secondary data analysis
from the 2017 MICS6 data set. Studies like this have been used for public
health planning, monitoring, and evaluation (Setia, 2016). Aspects of health
such as child mortality can and have been monitored with this method. To
conduct this study, a quantitative analysis of previously collected data was
done and inferences were drawn from that. The authors explained that with
cross-sectional studies, investigators measure both outcomes and exposures
in the study participants at the same time. A qualitative or mixed-methods
approach was not taken, because of this, the responses given were finite and
left little room for additional information to be shared with survey
administrators. With this design, outcomes were not altered or influenced by

50
interventions. The scope of this study focused on variables that align with the
RQs of this study.
Limitations
There were many limitations that impacted this study and its outcome.
Collection of accurate and reliable data on water treatment type, number of
households using toilets, location of water source, and location of toilet
facility may have been lacking due to the need for adequate training of data
collectors, ensuring consistency in measurements, and minimizing biases.
While conducting this study, I also discovered that the primary data
collection analysis person working with transcribing the data unexpectedly
died, leaving the transcription process unfinished. The data set may have
been limited based on people’s accessibility to the researchers and data
collectors. The data could have also been skewed based on participant
accessibility and locale. According to Headey and Palloni (2019), WASH
evaluations generally had poor compliance, rural bias, and limited exposure.
All of this was seen both in the way the data was collected as well as
transcribed. The authors also detailed the chance of excluding variables in
cross-sectional observational studies, creating a bias in itself (Headey and

51
Palloni, 2019). Self-reporting biases or recall errors by participants may have
also impacted the accuracy of the information.
Other limitations of this study included the use of secondary data and
how it was collected. The most important limitation with this data was its age
and how far removed it was from present day. This data was collected in
2016 and transcribed in 2017. Since this data was collected, the world has
been impacted by a global pandemic which could have impacted aspects of
both WASH and child mortality in Sierra Leone. Factors specific to the
context of Sierra Leone also limited the broader applicability of the results.
Significance
This study was significant in that limited availability of safe drinking
water, handwashing facilities, and sanitation services in Sierra Leone and
child mortality was a large public health issue. It held great significance as it
addressed the limited research on the availability of safe toilet facilities and
drinking water in Sierra Leone. Notably, WASH-related diseases had
contributed to a significant portion of deaths in Sierra Leone, accounting for
20% (Sesay et al., 2022). By examining the factors influencing the
availability of safe WASH practices, this study had the potential to contribute
to public health advancements and inform strategies to lower child mortality.

52
Access to improved toilet facilities and safe drinking water was crucial for
preventing waterborne diseases, reducing the risk of contamination, and
promoting overall community health. With only a small percentage of the
population having access to basic sanitation services, there was an urgent
need to understand the factors influencing this problem. The findings
contributed to understanding the dynamics involved in the availability of
toilet facilities and safe drinking water, providing insights for evidence-based
interventions and policy recommendations. Ultimately, the study sought to
improve public health outcomes by guiding efforts to enhance access to these
vital resources, leading to improved health and well-being in Sierra Leone
and similar contexts.
Summary and Conclusions
Child mortality was an important public health indicator of global
health, more so in developing countries, which many parts of sub-Saharan
Africa were categorized as (Amegbor & Addae, 2023). While rates of child
mortality have decreased over the last 3 decades, sub-Saharan Africa still
suffered from high rates of child mortality (Ezbakhe & Pérez Foguet, 2020).
The relationship between aspects of WASH and child mortality had been
researched, with much left to explore. This quantitative study aimed to

53
continue that research with respect to a particular country, Sierra Leone.
Using Urie Bronfenbrenner’s (1970) SEM, other factors such as area, wealth
index, education and sex of head of household were assessed as control
factors. In the next chapter, I described the research methodology, variables,
design and data collection procedures used.

54
Section 2: Research Design and Data Collection
Introduction
In Section 1, I discussed the history of WASH, specifically as it relates
to LMICs. The importance of this study and how this area has been relatively
unresearched in terms of the relationship between toilet facilities and
drinking water in Sierra Leone and child mortality was reviewed. The
individual factors of education, gender, area, and socioeconomic status in
relation to WASH and child mortality were looked at.
In this section, I provided a rationale for the chosen research design
and data source for this study. The rationale behind the chosen research
design and its importance in research success was elaborated upon. The study
population, area, data collection techniques, and instruments of use were
explored. The chosen theoretical framework was expanded upon, concluding
with potential threats to validity and ethical considerations.
Research Design and Rationale
For this quantitative study, I used a cross-sectional research design
utilizing secondary data from UNICEF’s MICS6. According to Kesmodel
(2018), a crosssectional study is identified by data collection at a specific
point in time. The MICS6 data was collected in 2016 and published in 2017.

55
The MICS6 household questionnaire was modified to include a new question
on the availability of drinking water correlating with the Joint Monitoring
Programme core questions (Bain et al., 2021). The data collected for the
MICS6 provided integral information on various factors related to water
sources, treatment, and sanitation facilities, determining how they played a
role in Sierra Leone’s child mortality rate. Variables of interest included the
independent variables of location
of water source, location of toilet facility, number of households using toilet
and water treatment type. The variables of area, wealth index, education, and
sex of head of household were used as independent variables for one
question and control variables for two questions with the dependent variable
being child mortality.
There were many advantages to a cross-sectional study using
secondary data. One of those advantages was that secondary data results can
be reproduced which speaks to both the integrity and validity of a study
(Bainter & Curran, 2015). Using secondary data also allowed for a better
understanding of changes over time that may be seen. In alignment with this
nuance were the benefits of cross-sectional studies which include estimates
of prevalence of disease, health knowledge and behaviors, and even

56
associations between variables (Kesmodel, 2018). These advantages along
with time saved due to not only data collection but expenses from travel and
boarding also spoke to the importance of secondary data use.
Methodology
According to Rasid (2022), choosing an appropriate research method
that aligns with the chosen problem is the first step in planning data
collection and analysis. Choosing a research method that aligns with the
chosen problem was a key component of research success. In this section, the
chosen methodology for this study was discussed as well as the study area
and population. The data collection techniques used along with the
instrumentation and operationalization of constructs were delved into. The
theoretical framework, data variables, description, and RQs were introduced
as well as the data analysis plan. I concluded this section with an explanation
of the planned statistical test and analysis, threats to internal and external
validity, and ethical procedures.
Population
Many factors impact the spread of infectious diseases and mortality in
subSaharan African countries like Sierra Leone. Some of those include

57
knowledge, socioeconomic status and resource accessibility, attitudes, and
practices related to
WASH. Sierra Leone is located on the western coast of Africa. With a
population of
8,800,000 (Worldometer, 2023) and a ranking of 182 out of 189 on the
Human Development Index, which measures average achievement in parts of
human development, Sierra Leone was a prime area of study (World Food
Programme, n.d.). While Sierra Leone’s population steadily increases, other
areas like education, income, and accessibility to basic necessities have in
fact decreased. Sierra Leone has endured several setbacks from a decades-
long war, Ebola in 2015, and the COVID-19 pandemic (World Food
Programme, n.d.). These adversities have continued to impact life
expectancy for adults and children alike.
Sierra Leone's child mortality rates are some of the highest worldwide
(CarshonMarsh et al., 2022). The reason behind this is unclear, which
explained the need to explore a basic human need for survival and an
influence on child mortality: WASH resources. Berthe et al. (2020) asserted
that one of the potential reasons for the mortality rates seen were poor
hygienic practices, inadequacy of water supply, and poor sanitary conditions.

58
In Sierra Leone, only 16% of the population has access to basic sanitation
services (UNICEF, n.d.-c). WASH resources are lacking in this part of the
world, leading some to believe there was a correlation between WASH
practices and child mortality. The impetus for conducting this study were
these alarming statistics presented by UNICEF, revealing that Sierra Leone,
and a significant portion of the global population lack access to safe drinking
water, handwashing facilities with soap, and adequate sanitation services,
highlighting a pressing social issue.
Sampling Procedures
To complete this study, I analyzed secondary data. Secondary data was
obtained from UNICEF’s MICS, specifically the MICS6 (S. Khan &
Hancioglu, 2019). MICS6 is an international household survey implemented
via collaboration efforts between
UNICEF, country ministries of health and statistics offices that has been used
since the 1990s to inform policy decisions and implement program
interventions geared towards improved health for women and children (Bain
et al., 2021; The World Bank, n.d.; WHO,
n.d.). The MICS is supposed to be conducted once every 3 to 5 years (Bain et
al., 2021).

59
The surveys are administered by national governments with technical
assistance from UNICEF during all stages to completion (Bain et al., 2021).
These are crosssectional surveys. According to Bain et al. (2021), the surveys
use a multistage stratified sampling approach of between 100 to 250
households randomly and clusters of 20–25 within certain areas. The random
selection of households is to ensure equal probability of selection amongst
areas. Interview teams generally include both men and women to conduct
same-sex interviews for any cultural or religious regions, a driver, supervisor,
and a measurer who takes height and weight measurements of the children
participants for the anthropometry module. These surveys collected
information and were a key source of data on water and sanitation, child
labor and protection issues, health of children and most recently, rapid water-
quality testing (Bain et al., 2021; S. Khan & Hancioglu, 2019; WHO, n.d.).
To initiate the water and sanitation portion of the module, a question about
the type of drinking water source predominately used by household members
followed by its location was asked (Bain et al., 2021). These factors and key
indicators make the MICS6 the most appropriate source to procure and
analyze secondary data from in relation to this study.

60
Sample Size and G*Power Analysis
The study sample size of 18,006 was larger than the minimum
recommended sample size based on G*Power analyses. According to Lakens
(2022), justifying a study sample size is important because it helps to explain
how the collected data is expected to provide valuable information. The
minimum sample size is the smallest number of participants needed for a
study. For this study, a confidence level of 95% was chosen, meaning that
95% of the time this study is run, the expectation is the results are the same.
A logistic regression z-test G*Power analysis was run for each RQ. The A
priori power analysis was conducted which computed the required sample
size when given the alpha, power, and effect size (Learn Statistics Easily,
2022). The minimum sample size for RQ1 was 136. The odds ratio was 2 for
all analyses as a large sample size was needed. From the Gebremichael et al.
(2021) article, a probability value of .5 was used. The R2 for RQ1 was
calculated at .052 after a regression analysis was conducted using the
independent variables. An R2 of .040 was used for the sample size calculation
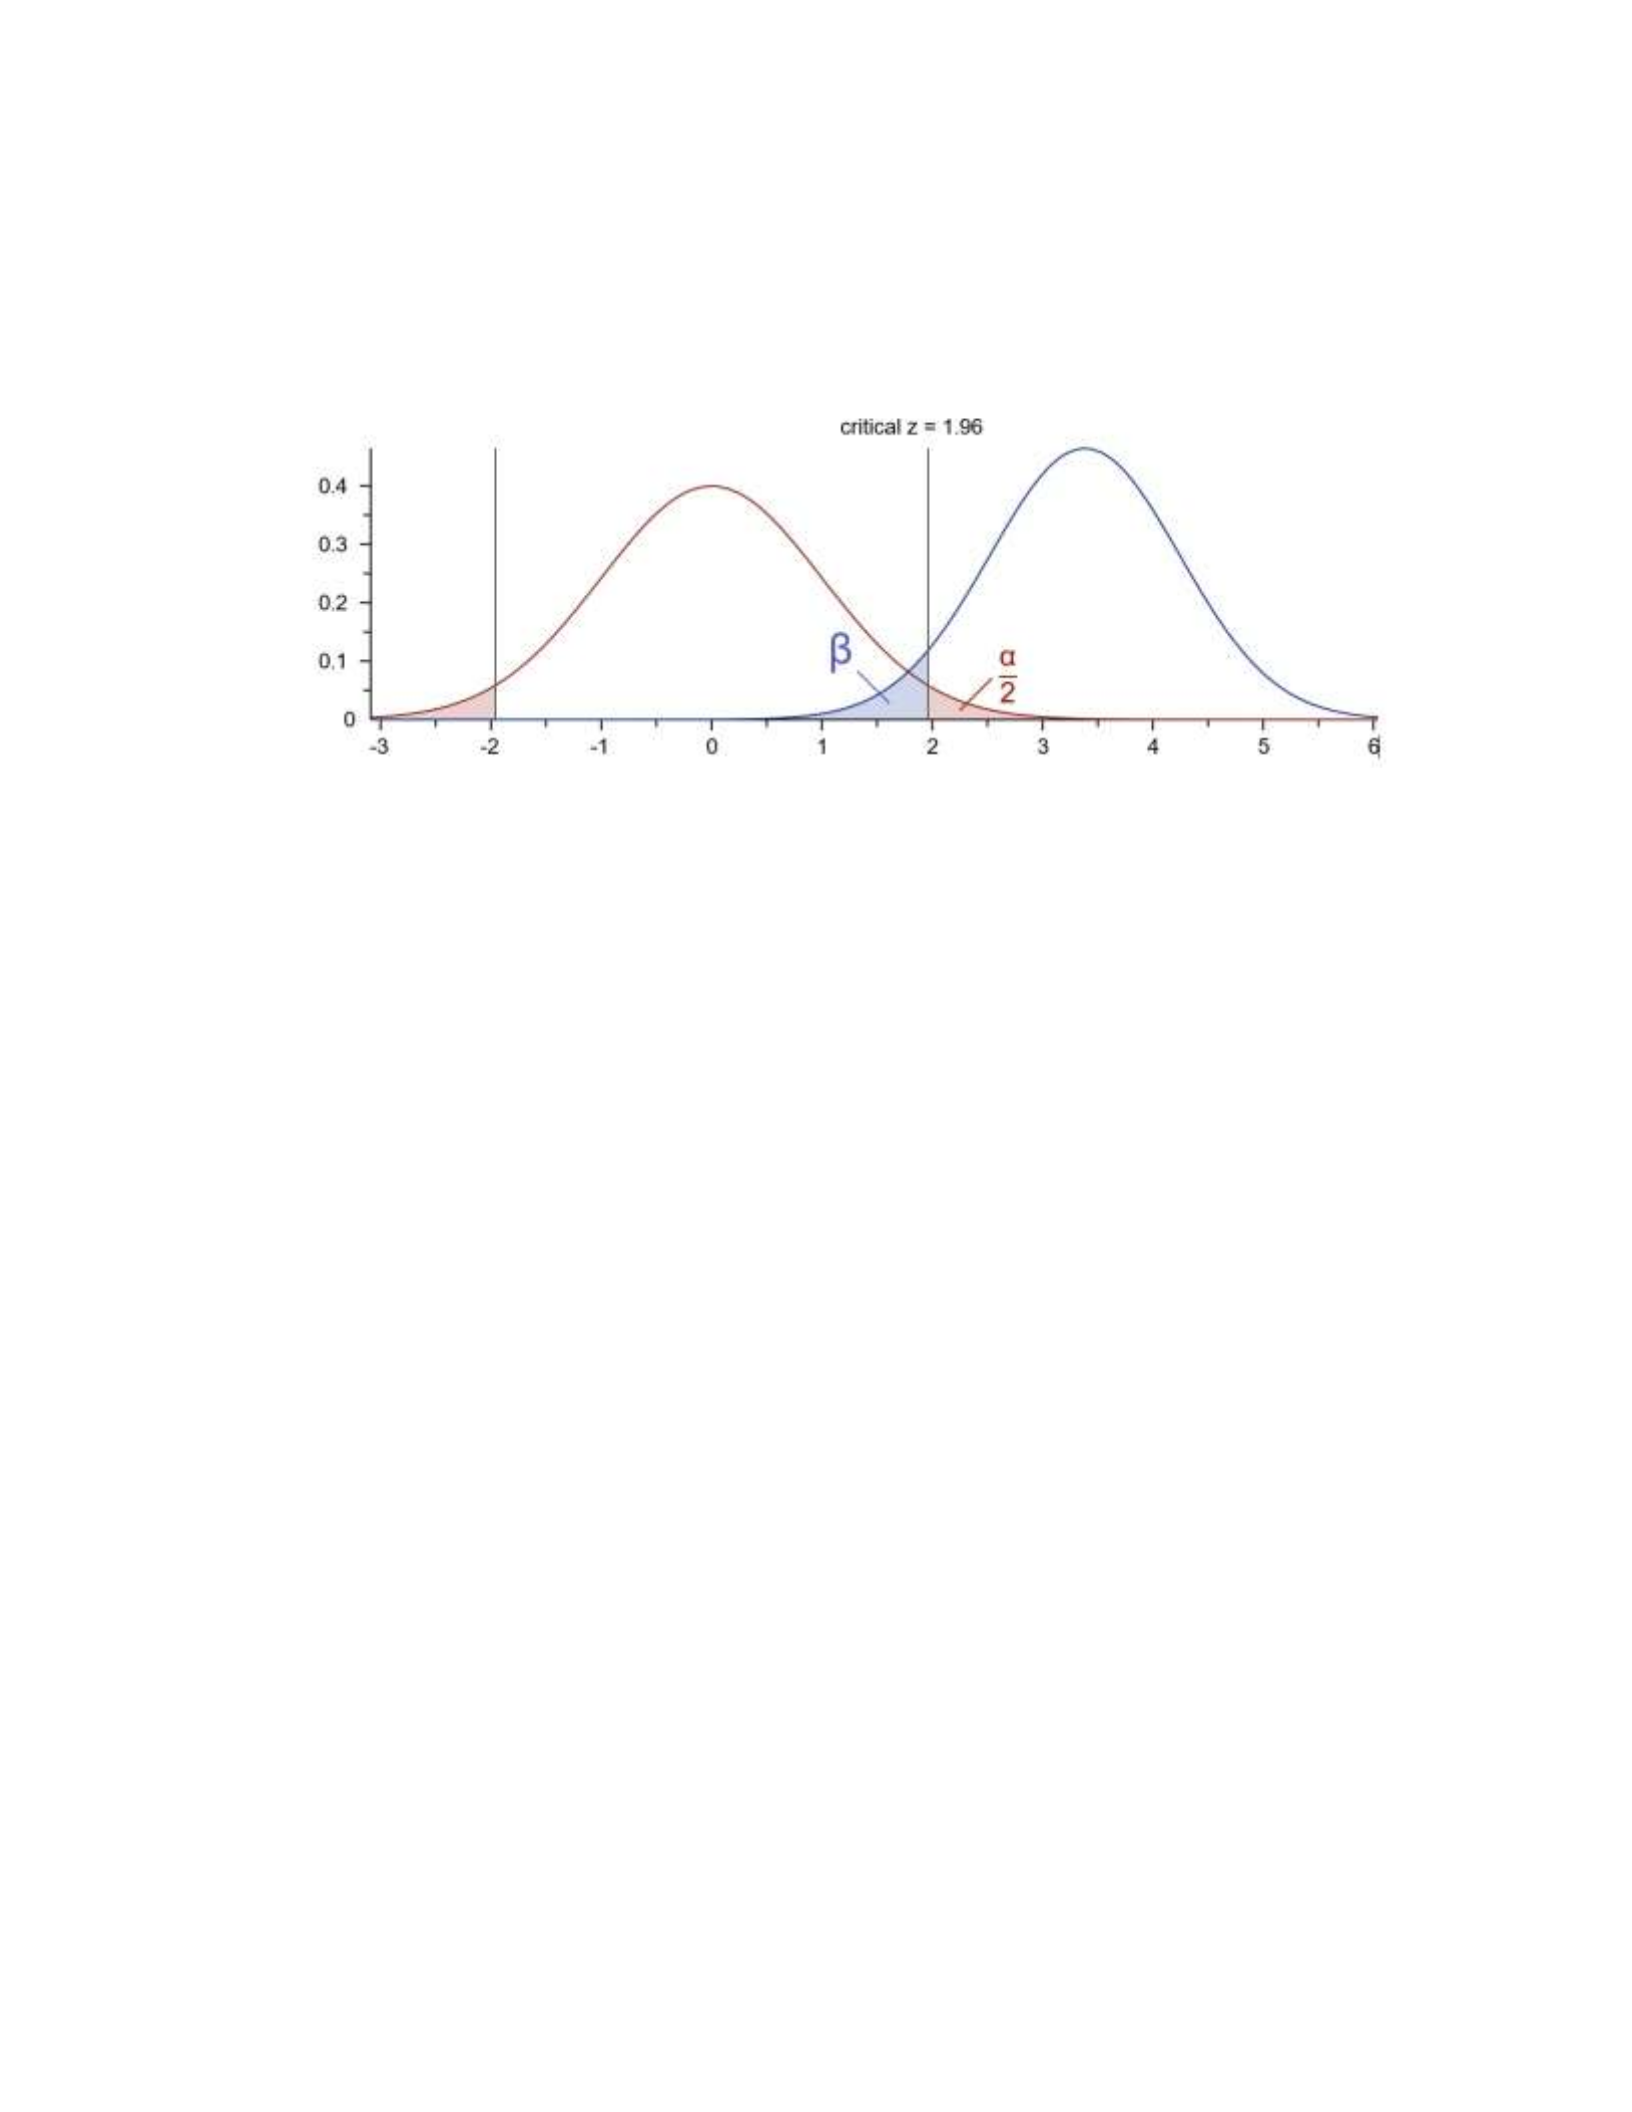
for RQ2, and R2= .002 was used for RQ3. Figure 3 shows the central and
noncentral distributions. RQs 2 and 3 had minimum sample size calculations
of 134 and 129, respectively.
61
Figure 3
G*Power Analysis for Minimum Sample Size
Instrumentation and Operationalization of Constructs
The 2017 MICS6 data set contained the study variables used in this
study. The
MICS6 employed the use of several instruments that aided in answering this
studies RQs. The MICS6 survey uses structured questionnaires to gather
information from households, ensuring standardized data collection. The
specific data collection instruments used within the MICS6 survey for water
and sanitation indicators included a household questionnaire, water quality
testing and observational checklists. The questionnaire captured data on
household characteristics, including key variables to this study such as
location of water source, location of toilet facility, water treatment type,
number of households using toilet, area, wealth index, education, sex of
head of household and child mortality. Water quality testing instruments

62
were used to assess the microbial and chemical quality of water sources,
including measures of water safety, contamination levels and observational
checklists to physically inspect and record the condition and functionality of
sanitation facilities, including toilet types, presence of handwashing stations,
and overall hygiene practices. Similar instrumentation and
operationalization of constructs were used in (Ademas et al., 2021)’s
community-based cross-sectional study in Ethiopia regarding WASH’s
impact on children under 5 years of age. Based on the similarity in data
collection techniques, these data collection instruments within the MICS6
survey were assumed to provide information necessary to address the RQs.
The operationalization of the study variables is presented in the following
subsections.
Predictor Variable 1: Location of Water Source
The descriptive variable of location of water source was assessed
using a single item that queried the location of participant’s water source.
Location of water source is an ordinal variable which was coded as follows:
1 = in own dwelling, 2 = in own yard/plot,
3 = elsewhere, and 9 = no response.

63
Predictor Variable 2: Location of Toilet Facility
The descriptive variable of location of toilet facility was assessed
using a single item that queried the location of participants toilet facility.
Location of toilet facility was an ordinal variable, which was coded as
follows: 1 = in own dwelling, 2 = in own yard/plot, 3 = elsewhere, and 9 =
no response.
Predictor/Control Variable 3: Area
The descriptive variable of area was assessed using a single item on
where participants live. This was a dichotomous variable with 1 = urban and
2 = rural.
Predictor/Control Variable 4: Wealth Index
The descriptive variable of wealth index was assessed using a single
item that queried the participant’s level of wealth. Wealth index was an
ordinal variable and was coded as follows: 1 = poorest, 2 = second, 3 =
middle, 4 = fourth, and 5 = richest.
Predictor/Control Variable 5: Education of Head of Household
The descriptive variable of education of head of household was
assessed using a single item that queried the participant’s level of education.
Education of head of household was an ordinal variable coded where 0 =

64
preprimary or none, 1 = primary, 2 = lower secondary, 3 = upper secondary+,
and 9 = missing/don’t know.
Predictor/Control Variable 6: Sex of Head of Household
The descriptive variable of sex of head of household was assessed
using a single item on the participant’s gender. This variable was measured
as follows: 1 = male, 2 = female, and 9= missing.
Outcome Variable: Child Mortality
The outcome variable of ever had a child who later died, relabeled as
child mortality was assessed using a single item on child mortality. This is a
dichotomous variable with 1 = yes and 2 = no. The variable was however
recoded so that 0 represented no child mortality and 1 represented child
mortality.
The independent variables of sex of head of household, wealth index,
education, and area were used as control variables for RQs 2 and 3. Location
of water source and location of toilet facility were used as the independent
variables for question two as well.
Child mortality was the outcome variable for all questions. For question 3,
there were two alternative predictor variables.

65
Predictor Variable 7: Water Treatment Type
The descriptive variable of water treatment type was assessed using a
multi-item variable that queried about how participant’s treat their water.
Water treatment type was initially coded where each water treatment was
separated and dichotomously measured as follows: ? = no response, A = boil,
B = add bleach/chlorine, C = strain it through a cloth, D = use water filter, E
= solar disinfection, F = let it stand and settle, X = other, Z = don't know, and
NR = no response. As these were string variables, each was individually
recoded with 0 representing system missing answers and 1= the water
treatment type of use. Each water treatment type was treated as an individual
independent variable. As “no response” would provide no response would
provide no information on the impact water treatment type plays on child
mortality, it was excluded from the final analysis. The newly created
variables were once again recoded into one variable labeled “water
treatment” where the number of water treatments used were combined to
show how many water treatments were used, if any. The variable was
measured as follows: 0 = no response, 1 = one water treatment, 2 = two water
treatments, and 3 = three water treatments.

66
Predictor Variable 8: Number of Households Using Toilet Facility
The descriptive variable of number of households using toilet were
assessed using a single item that queried for number of households using a
single toilet. Number of households using toilet was an ordinal variable
coded where 2 = two, 3 = three, 4 = four,
5 = five, 6 = six, 7 = seven, 8 = eight, 9 = nine, and 10 = 10 or more
households.
Data Analysis Plan
I developed the following RQs and corresponding hypotheses to
address the identified problem:
RQ1: Is there an association between location of water source, location
of toilet facility, area, wealth index, education, and sex of head of household
on child mortality in Sierra Leone?
H01: There is no association between location of water source, location
of toilet facility, area, wealth index, education, and sex of head of
household on child mortality in Sierra Leone.
HA1: There is an association between location of water source,
location of toilet facility, area, wealth index, education, and sex of
head of household on child mortality in Sierra Leone.

67
RQ2: Is there an association between the location of water source,
location of toilet facility and child mortality in Sierra Leone, when
controlling the factors of sex of head of household, wealth index, education,
and area?
H02: There is no association between the location of water source,
location of toilet facility and child mortality in Sierra Leone, when
controlling the factors of sex of head of household, wealth index,
education, and area.
HA2: There is an association between the location of water source,
location of toilet facility and child mortality in Sierra Leone, when
controlling the factors of sex of head of household, wealth index,
education, and area.
RQ3: Is there an association between water treatment type, number of
households using toilet facility and child mortality in Sierra Leone, when
controlling the factors of sex of head of household, wealth index, education,
and area?
H03: There is no association between water treatment type, number of
households using toilet facility and child mortality in Sierra Leone,

68
when controlling the factors of sex of head of household, wealth
index, education, and area.
HA3: There is an association between water treatment type, number of
households using toilet facility and child mortality in Sierra Leone,
when controlling the factors of sex of head of household, wealth
index, education, and area.
To answer the RQs, I used IBM SPSS Version 29. SPSS Version 29 is
a predictive analytics software created by IBM that allows for the analysis of
primary or secondary data to predict outcomes within a certain level of
confidence (Walden
University, n.d.). To answer all RQs, a binomial logistic regression was
conducted. Logistic regression derives from the logistic function which
originated in the 19th century by Pierre François Verhulst to detail the growth
of human populations (Boateng & Abaye, 2019). This regression analysis
relied on an outcome/dependent variable that was dichotomous, meaning
there were only two possible outcomes and one or more independent
variables (Das, 2021; Prasetyo et al., 2020). This analysis method estimated
the probability of an outcome’s occurrence. A binary logistic regression
analysis depends on the following key assumptions: a dichotomous
dependent variable; one or more independent variables; independent

69
observations, meaning a variable is not influenced by other observations;
little or no multicollinearity, meaning the independent variables should not
be highly correlated with one another; a linear relationship between
continuous variables and the log odds of the dependent variable; and, finally,
no significant outliers in the data set (Harris 2021; Statistics Solutions, n.d.).
For RQ1, there were six independent variables: location of water
source, location of toilet facility, area, wealth index, education of head of
household, and sex of head of household with child mortality as the
dependent variable. The independent variables for RQ2 were location of
water source and location of toilet facility. The independent variables for
RQ3 were water treatment type and number of households using toilet
facility. The dependent variable for all questions was child mortality and the
factors of sex of head of household, wealth index, education of head of
household, and area were control variables in questions two and three.
This analysis method can lead to determining how exposure to systems
can influence outcomes, which was child mortality for this study. This
method of analysis allowed for the exploration of multiple variables
simultaneously, enabling an understanding of the complex interactions

70
between drinking water, sanitation facilities, and child mortality in Sierra
Leone.
Threats to Validity
With every study, there are seen and unseen threats that may interfere
with the validity of research that should be considered. One of the potential
threats to this study’s validity was sampling bias. Sampling bias can impact
the generalization of study results (S.-W. Chen et al., 2022). This was a
strong possibility as resources could potentially be limited based on rural/
urban living, education, gender, and socioeconomic status, all of which was
analyzed in this study. When surveys are conducted, data collection is done
using one method or another such as phone calls or internet-based
questionnaires (S.-W. Chen et al., 2022). This could have hindered some in
Sierra Leone from being able to participate due to accessibility limitations.
The quality of primary research is a critical threat to validity. Sierra
Leone’s current adult literacy rate is 47.7%, 4.5% higher than it was in 2018
(Sierra Leone Literacy Rate 2004-2023, n.d.). Participant’s understanding of
the questionnaire heavily influenced both responses and nonresponses.
Another threat to validity was the use of Water Quality Testing. The MICS6
was the official rollout of the tool for over 40 MICS6 surveys, generating

71
nationally representative data on water quality for the first time in many
places (UNICEF, 2018). While thorough manuals were distributed to field
teams, it would not have prevented errors in water quality testing as the pilot
program. Finally, as stated earlier, according to a data analytics specialist
with UNICEF, the data transcription process was halted and not completed
due to the death of a member of the team working on this set of data,
ultimately threatening the validity and integrity of the data.
Ethical Procedures
I obtained permission to access Sierra Leone’s MICS6 data from the
Walden University Institutional Review Board. This assisted in protecting the
integrity of the study. Tripathy (2013) asserted that data that have no
identifying information do not need to be fully scrutinized by an ethics
review board. The MICS6 authors used alias ID numbers for participants to
prevent biases and create the best environment to appropriately determine the
causal impact of health interventions (Sidani & O’Rourke, 2020). The data's
origin was clearly stated. Even though the data were freely available, I
obtained approval to protect the efficacy of all research results. Another
source of ethical procedures was ensuring that participation in the surveys
was not mandatory and was done at the discretion of participants. According

72
to Statistics Sierra Leone (2018), participants were informed of their right to
refuse to answer any questions and stop the interview at any time. Verbal
consent was received from all participants and their children. Participants
were also informed of that participation was voluntary and the aspects of
confidentiality and anonymity of information that went with participating
(Statistics Sierra Leone, 2018).
Summary
This section focused primarily on the chosen research design, data
source, and how that data was obtained. The chosen research design,
elaborating on the advantages of a cross-sectional study and the rationale
behind the selection were discussed. The importance of choosing the
appropriate methodology for this research study’s success was further
considered. The study population and area were reiterated as was the
immediate need for this study. The data collection techniques,
instrumentation, and operationalization of constructs that were used as well
as the conceptual framework, data variables, RQs, the planned statistical test,
and data analysis were detailed. This section concluded with potential threats
to validity and ethical considerations. In the next section, the results and
findings of the analysis are presented.

73

74
Section 3: Presentation of the Results and Findings
The purpose of this quantitative cross-sectional study was to examine
the impact of WASH on child mortality in Sierra Leone. The results of this
study can lead to policy changes that improve the general well-being of the
population. This study can also be used to improve health outcomes with
respect to the other variables studied: wealth, sex of head of household,
education of head of household and area. The results could also be used to
improve health outcomes among diabetic patients. The RQs and hypotheses
for this study were the following:
RQ1: Is there an association between location of water source, location
of toilet facility, area, wealth index, education, and sex of head of household
on child mortality in Sierra Leone?
H01: There is no association between location of water source, location
of toilet facility, area, wealth index, education, and sex of head of
household on child mortality in Sierra Leone.
HA1: There is an association between location of water source,
location of toilet facility, area, wealth index, education, and sex of
head of household on child mortality in Sierra Leone.

75
RQ2: Is there an association between the location of water source,
location of toilet facility and child mortality in Sierra Leone, when
controlling the factors of sex of head of household, wealth index, education,
and area?
H02: There is no association between the location of water source,
location of toilet facility and child mortality in Sierra Leone, when
controlling the factors of sex of head of household, wealth index,
education, and area.
HA2: There is an association between the location of water source,
location of toilet facility and child mortality in Sierra Leone, when
controlling the factors of sex of head of household, wealth index,
education, and area.
RQ3: Is there an association between water treatment type, number of
households using toilet facility and child mortality in Sierra Leone, when
controlling the factors of sex of head of household, wealth index, education,
and area?
H03: There is no association between water treatment type, number of
households using toilet facility and child mortality in Sierra Leone,

76
when controlling the factors of sex of head of household, wealth
index, education, and area.
HA3: There is an association between water treatment type, number of
households using toilet facility and child mortality in Sierra Leone, when
controlling the factors of sex of head of household, wealth index, education,
and area. In Section 3, the secondary data set, demographic data for the
sample, statistical assumptions, logistic regression results, and moderation
analysis results is discussed.
Assessing the Data Set for Secondary Data Set
Data Collection
After obtaining approval from the Walden University Institutional
Review Board, I downloaded the 2017 Sierra Leone MICS6 data set was
from UNICEFs website for analysis. It was the most recent data set available
with the MICS7 currently in the developmental stage. The data set included
10 data files, ranging from 48 to 534 variables and from 7,534 to 75,015
cases depending on the data file (The World Bank, n.d.).
Discrepancies of Secondary Data Set
Unfortunately, the data set had several discrepancies. Of those
discrepancies was the completeness of the different data files. Many of the

77
variables used for this study had more non-responses than responses,
potentially skewing the outcome of the variables. Another discrepancy was
the water type variable; the variable in the data set was originally a string
variable. As such, it had to be recoded twice to become usable for this study.
The missing responses also had to be accounted for so SPSS could recognize
the missing data and exclude them from the regression analysis.
Demographic Characteristics of the Sample
Data was collected from residents in rural and urban areas of Sierra
Leone. Regions included the eastern providences of Kono, Kenema, and
Kailahun; the northern providences of Bombali, Kambia, Koinadugu, Port
Loko, and Tonkolili; the southern providences of Bo, Bonthe, Moyamba, and
Pujehum, as well as urban and rural areas in the western portion of the
country. For this study, the demographics looked at were area, sex of head of
household, education of head of household, and wealth index quartile. The
categories for area were simplified and represented as 1= urban and 2= rural.
The categories for sex of head of household were represented as 1= male and
2= female. The categories for education of head of household were
represented as 0= preprimary or none, 1= primary, 2= lower secondary and

78
3= upper secondary +. The categories for wealth index were represented as
1= poorest, 2= second, 3= middle, 4= fourth and 5= richest.
Table 1 summarizes the demographic characteristics for the area variable. Of
the 18,006 participants, 10,816 were in a rural areas, and 7,135 were in an
urban one.
Table 1
Participant Demographics: Area Type
Area type
f
%
Urban
7,135
39.6
Rural
10,816
60.1
Missing
55
0.3
Total
18,006
100
Table 2 summarizes the sex of head of household variable used for this
study. More than half of the 18,006 participants, 10,506 (58.3%), self-
identified as male, whereas 4,803 (26.7%) self-identified as female; 2,697
(15%) participants did not selfidentify as either male or female.
Table 2
Participant Demographics: Sex of Head of Household
Sex
f
%
Male
10,506
58.3
Female
4,803
26.7

79
Missing
2,697
15.0
Total
18,006
100
Table 3 looks at the categorization of education as selected by the
deemed head of household. More than half of the participants, 9,347
(51.9%), listed their level of education as preprimary or none. The lowest
education level attained was primary (n=
1,459, 8.1%), followed closely by lower secondary (n= 1,502, 8.3%).
Table 3
Participant Demographics: Education of Head of Household
Education level
f
%
Preprimary or none
9,347
51.9
Primary
1,459
8.1
Lower secondary
1,502
8.3
Upper secondary+
2,984
16.6
Missing
2,714
15.1
Total
18,006
100
Table 4 summarizes the wealth index variable used for this study. Less
than 6% separated the highest and lowest reported wealth index. Poorest was
the most prevalent wealth index (n = 4,029, 22.4%). Tied at 21.1% were
second (n = 3,799) and middle (n =
3,795). The lowest reported wealth index was fourth (n = 3,060, 17%).

80
Table 4
Participant Demographics: Wealth Index
Wealth index level
f
%
Poorest
4,029
22.4
Second
3,799
21.1
Middle
3,795
21.1
Fourth
3,060
17.0
Richest
3,190
17.7
Missing
133
0.7
Total
18,006
100
The main variables being observed pertain to WASH. Table 5
summarizes the demographic characteristics of the location of water source
variable used for the study. There were n= 13,8219 (73.4%) participants who
reported the location of their water source being somewhere other than their
home (elsewhere) and n= 177 (1%) participants who reported having a water
source in their home (in own dwelling).
Table 5
Participant Demographics: Location of Water Source
Water source
f
%
In own dwelling
177
1.0
In own yard
1,497
8.3
Elsewhere
13,219
73.4
Missing
3,113
17.3
Total
18,006
100

81
Table 6 summarizes the demographic characteristics of the location of
toilet facility variable used for the study. There were n= 7,732 (42.9%)
participants who reported the location of their toilet facility being in their
own yard and n= 1,214 (6.7%) participants who reported having a water
source in their home (in own dwelling).
Table 6
Participant Demographics: Location of the Toilet Facility
Location of toilet facility
f
%
In own dwelling
1,214
6.7
In own yard
7,732
42.9
Elsewhere
3,010
16.7
Missing
6,050
33.6
Total
18,006
100
Table 7 looks at the distribution of number of households that use one
toilet facility. The highest reported was n= 1,787 (9.9%) with three
households sharing a toilet facility. The lowest reported was n= 90 (.5%) at
ten or more households.
Table 7
Participant Demographics: Households Using Toilet Facility
No. of households using toilet facility
f
%
Two
1,375
7.6
Three
1,787
9.9
82
Four
1,334
7.4
Five
923
5.1
Six
564
3.1
Seven
453
2.5
Eight
240
1.3
Nine
113
0.6
Ten or more households
872
4.8
Don’t know
90
0.5
Missing
10,255
57.0
Total
18,006
100
Table 8 shows the original distribution of water treatment types. Each
was transcribed dichotomously as water treatment type or no response. As
shown, bleach/chlorine, n = 818 (4.5%) participants represented the largest
group in this study who answered the question pertaining to water treatment
type. There were n = 3 (0%) and n= 5 (0%) participants who did not know or
used solar as their water treatment type respectively. There were n= 16,022
participants who did not answer the question, accounting for 89% of
participants.
Table 8
Participant Demographics: Water Treatment Type
Water treatment type
Boil
90
0.5
Bleach/chlorine
818
4.5
Strain
439
2.4
f
%

83
Filter
47
0.3
As shown in Table 9, the water treatment variable was recoded to
reflect that a water treatment type is used and not necessarily, which type.
With this recode, it can be seen that some participants use more than one
water treatment type. There were n= 1,494 (8.3%) participants who used one
water treatment type. There were n= 19 (0.1%) participants who used three
water treatments. Many participants, n= 16, 276 (90.4%) failed to report any
water treatment method.
Table 9
Participant Demographics: Number of Water Treatment Methods
No. of water treatment methods
f
%
One
1,495
8.3%
Two
216
1.2%
Three
19
0.1%
Missing
16,276
90.4%
Total
18,006
100%
As shown in Table 10, n= 14,530 (80.7%) of participants reported not
experiencing child death, while n= 3,343 (18.6%) reported having
Solar
5
0
Let it stand
534
3
Other
48
0.3
Don't know
3
0
Missing
16022
89
Total
18006
100

84
experienced child death. There were n= 3,343 (18.6%) participants who
reported experiencing child death.
Table 10
Participant Demographics: Child Mortality
No child death 14,530 80.7
One or more child deaths 3,343 18.6
Missing 133 0.7
Total 18,006 100
Sample Representativeness
When designing a study, the chosen sample size is very important. The
justification for sample size speaks to how collected data impacts the overall
goal of a researcher (Lakens, 2022). A study sample is considered
representative of the population when the results of the study can be
generalized (Rudolph et al., 2023). Generalizability is possible when the
distribution of study variables is same as the target population, which is an
expectation with random sampling. A sample larger than needed allows for
more accurate results (Andrade, 2020). The author stated that most study’s
use 80% as the marker for a statistically significant outcome to be true to the
study population.
No.
of c
hild death
s
f
%

85
Others may use 90% and a p-value of 0.05. or 0.01. For this study, 95% was
used. Rudolph et al. (2023) concluded that being able to generalize a study
aligns with sample representativeness.
Results
Descriptive Statistics
A total of 18,006 participants were included in this study. Table 11
shows the means, standard deviations, and frequencies for participants who
answered each question about the specific variables. The means and standard
deviations were as follows: location of the water source (M = 2.88, SD =
.364), location of the toilet facility (M = 2.15, SD =
.575), household using this toilet facility (M = 5.82, SD = 10.300), water
treatment method (M = 1.15, SD = .384), wealth index (M = 2.86, SD =
1.408), sex of head of household (M = 1.31, SD = .464), area (M = 1.60, SD
= .489), education of head of household (M = .88, SD = 1.215), and child
mortality (M = .19, SD = .390).
Table 11
Descriptive Statistics for the Study Variables
Variable
n
M
SD
Location of the water source
14,893
2.88
.364
Location of the toilet facility
11,956
2.15
.575
Households using toilet facility
7,751
5.82
10.300

86
Water treatment method
1,730
1.15
.384
Wealth index
17,873
2.86
1.408
Sex of head of household
15,309
1.31
.464
Area
17,951
1.60
.489
Education of head of household
15,292
.88
1.215
Child mortality
17,873
.19
.390
Statistical Assumptions
For a binary logistic regression, there are six assumptions that should
not be violated. Those assumptions are as follows: a dichotomous dependent
variable, one or more independent variables, which can either be categorical
or continuous, independent observations, a linear relationship between the
continuous variables and the log odds of the dependent variable, no
multicollinearity among independent variables and no significant outliers in
the data set. Each of these assumptions was tested with respect to the study
variables.
Assumption 1
Assumption 1 of a binary logistic regression is a dichotomous
dependent variable. As seen in Table 10, the study dependent variable, child
mortality, was measured dichotomously as either yes or no, not violating
Assumption 1 of the analyses.

87
Assumption 2
Assumption 2 of a binary logistic regression is having one or more
independent variables that are either continuous or categorical. As seen in
Tables 1–9, the independent variables used for the study fell into the category
of either categorical or continuous, thus, not violating Assumption 2 of the
analysis.
Assumption 3
Assumption 3 of a binary logistic regression is the independence of
observations. To test this assumption, a Durbin-Watson test was run for all
RQs. A Durbin-Watson value of 2 or below indicates independence of
observations. Two analyses were run: one for RQs 1 and 2, which had the
same variables, and another for RQ3 (see results in Tables 12 and 13). The
first analysis produced a Durbin-Watson value of 1.825 and the other a value
of 1.934. As both were in an acceptable range (Bobbitt, 2021), Assumption
3 was not violated.
Table 12
Durbin-Watson Test Results for Research Questions 1 and 2
Model
R
R2
Adjusted R2
SE of the
estimate
Durbin-
Watson
1
.102 a
.010
.010
.398
1.825

88
a The predictors (constant) were education of household head, wealth index,
location of the water source, sex of household head, location of the toilet
facility, and area. The dependent variable was child mortality.
Table 13
Durbin-Watson Test Results for Research Question 3
Model
R
R2
Adjusted R2
SE of the
estimate
Durbin-
Watson
1
.102 a
.010
.004
.388
1.934
a The predictors (constant) were households using toilet facility, education of
household head, area, water treatment method, sex of household head, and
wealth index. The dependent variable was child mortality.
Assumption 4
Assumption 4 of a binary logistic regression states that there should be
a linear relationship between continuous variables and the log odds of the
dependent variable (Statistics Solutions, n.d.). RQs 1 and 2 had no
continuous variables, so a test of linearity was not conducted. However, RQ3
had a continuous variable, thus, a logistic regression was conducted after
transforming the water treatment variable and creating a lane function for log
variable from it. As shown in Table 14, a calculated p-value of .298 shows
89
linearity between the continuous variable and log odds, so Assumption 4 was
not violated (FAQ: How Do I Interpret Odds Ratios in Logistic Regression?,
n.d.).
Table 14
Test of Linearity
Variable B SE Wald df p Exp(B) 95% CI for
EXP(B)
LL
UL
Water treatment method
3.362
3.152
1.137
1
.286
28.848
.060
13915.279
Households using toilet
facility
-.005
.013
.154
1
.695
.995
.969
1.021
LN_WT by Water
treatment method
-
2.286
2.196
1.083
1
.298
.102
.001
7.528
Constant
-
4.839
3.163
2.341
1
.126
.008
Note. CI = confidence interval; UL = upper limit; LL = lower limit. a
Variables entered on Step 1 were water treatment method, households
using toilet facility, LN_WT * Water treatment method.
Assumption 5
Assumption 5 states that there should be no multicollinearity among
independent variables. To test this assumption, a correlation was run for the

90
independent variables of each study question. Multicollinearity is defined as:
weak correlation 0<=|r|< 0.3, moderate correlation 0.3≤|r|<0.7 and a strong
correlation |r|>=7 (Vatcheva & Lee, 2016).
Location of water source showed a weak correlation with location of the
toilet facility for RQs 1 and 2 and a weak correlation between location of
water and sex of head of household, area and education of head of household
for RQ1 (see Tables 15 and 16). In addition, location of toilet facility showed
a moderate correlation with area. Wealth index and education of head of
household also showed a moderate correlation. The independent variables for
RQ3 showed no multicollinearity (see Table 17).
Table 15
Research Question 1 Correlations
Variable
Location of
the water
source
Location of
the toilet
facility
Wealth
index
Sex of head
of household
Area
Education of
head of
household
Location of the
water source
r
p (2-
tailed)
1
.198**
<.001
-.005
.505
-.025**
.003
.020*
.014
-.120**
<.001
n
14,893
11,581
14,802
14,893
14,853
14,876
Location of the
toilet facility
r p
(2tailed)
.198**
<.001
1
-.023*
.012
.007
.436
.031**
<.001
-.214**
<.001
n
11,581
11,956
11,867
11,956
11,919
11,941
Wealth index
r
-.005
-.023*
1
.009
-.761**
.037**
p (2tailed)
.505
.012
.258
<.001
<.001

91
n
14,802
11,867
17,873
15,211
17,873
15,194
Sex of head of
household
r p
(2tailed)
-.025**
.003
.007
.436
.009
.258
1
-.009
.245
-.176**
<.001
n
14,893
11,956
15,211
15,309
15,266
15,292
Area
r
.020*
.031**
-.761**
-.009
1
-.057**
p (2tailed)
.014
<.001
<.001
.245
<.001
n
14,853
11,919
17,873
15,266
17,951
15,249
Education of
head of
household
r p
(2tailed)
-.120**
<.001
-.214**
<.001
.037**
<.001
-.176**
<.001
-.057**
<.001
1
n
14,876
11,941
15,194
15,292
15,249
15,292
**. Correlation is significant at the 0.01 level (2-
tailed).
*. Correlation is significant at the 0.05 level (2-
tailed).
Table 16
Research Question 2 Correlations
Variable Location of the toilet Location of the water
facility source
Location of the
toilet facility
r
p (2-
tailed)
1
.198*
<.001
n
11,956
11,581
Location of the
water source
r p
(2tailed)
.198*
<.001
1

92
n
11,581
14,893
*. Correlation is significant at the 0.01 level (2-tailed).
Table 17
Research Question 3 Correlations
Variable
Households using toilet
facility
Water
treatment
method
Households using
toilet facility
r 1
p (2-
tailed)
-.023
.477
n 7,751
920
Water treatment
method
r -.023
1
p (2- .477 tailed)
n 920
1,730
Assumption 6
Assumption 6 of a binary logistic regression states that there should be
no significant outliers in the data set. To test this assumption, I performed a
regression analysis for all RQs. Figures 4 and 5 show the outliers of the
regression analyses. There were 98 outliers for RQ1 and RQ2 combined and
37 in RQ3. These outliers were considered to be significant as they all have a
z-residual of over 2.50. As significant outliers were found, Assumption 6 is
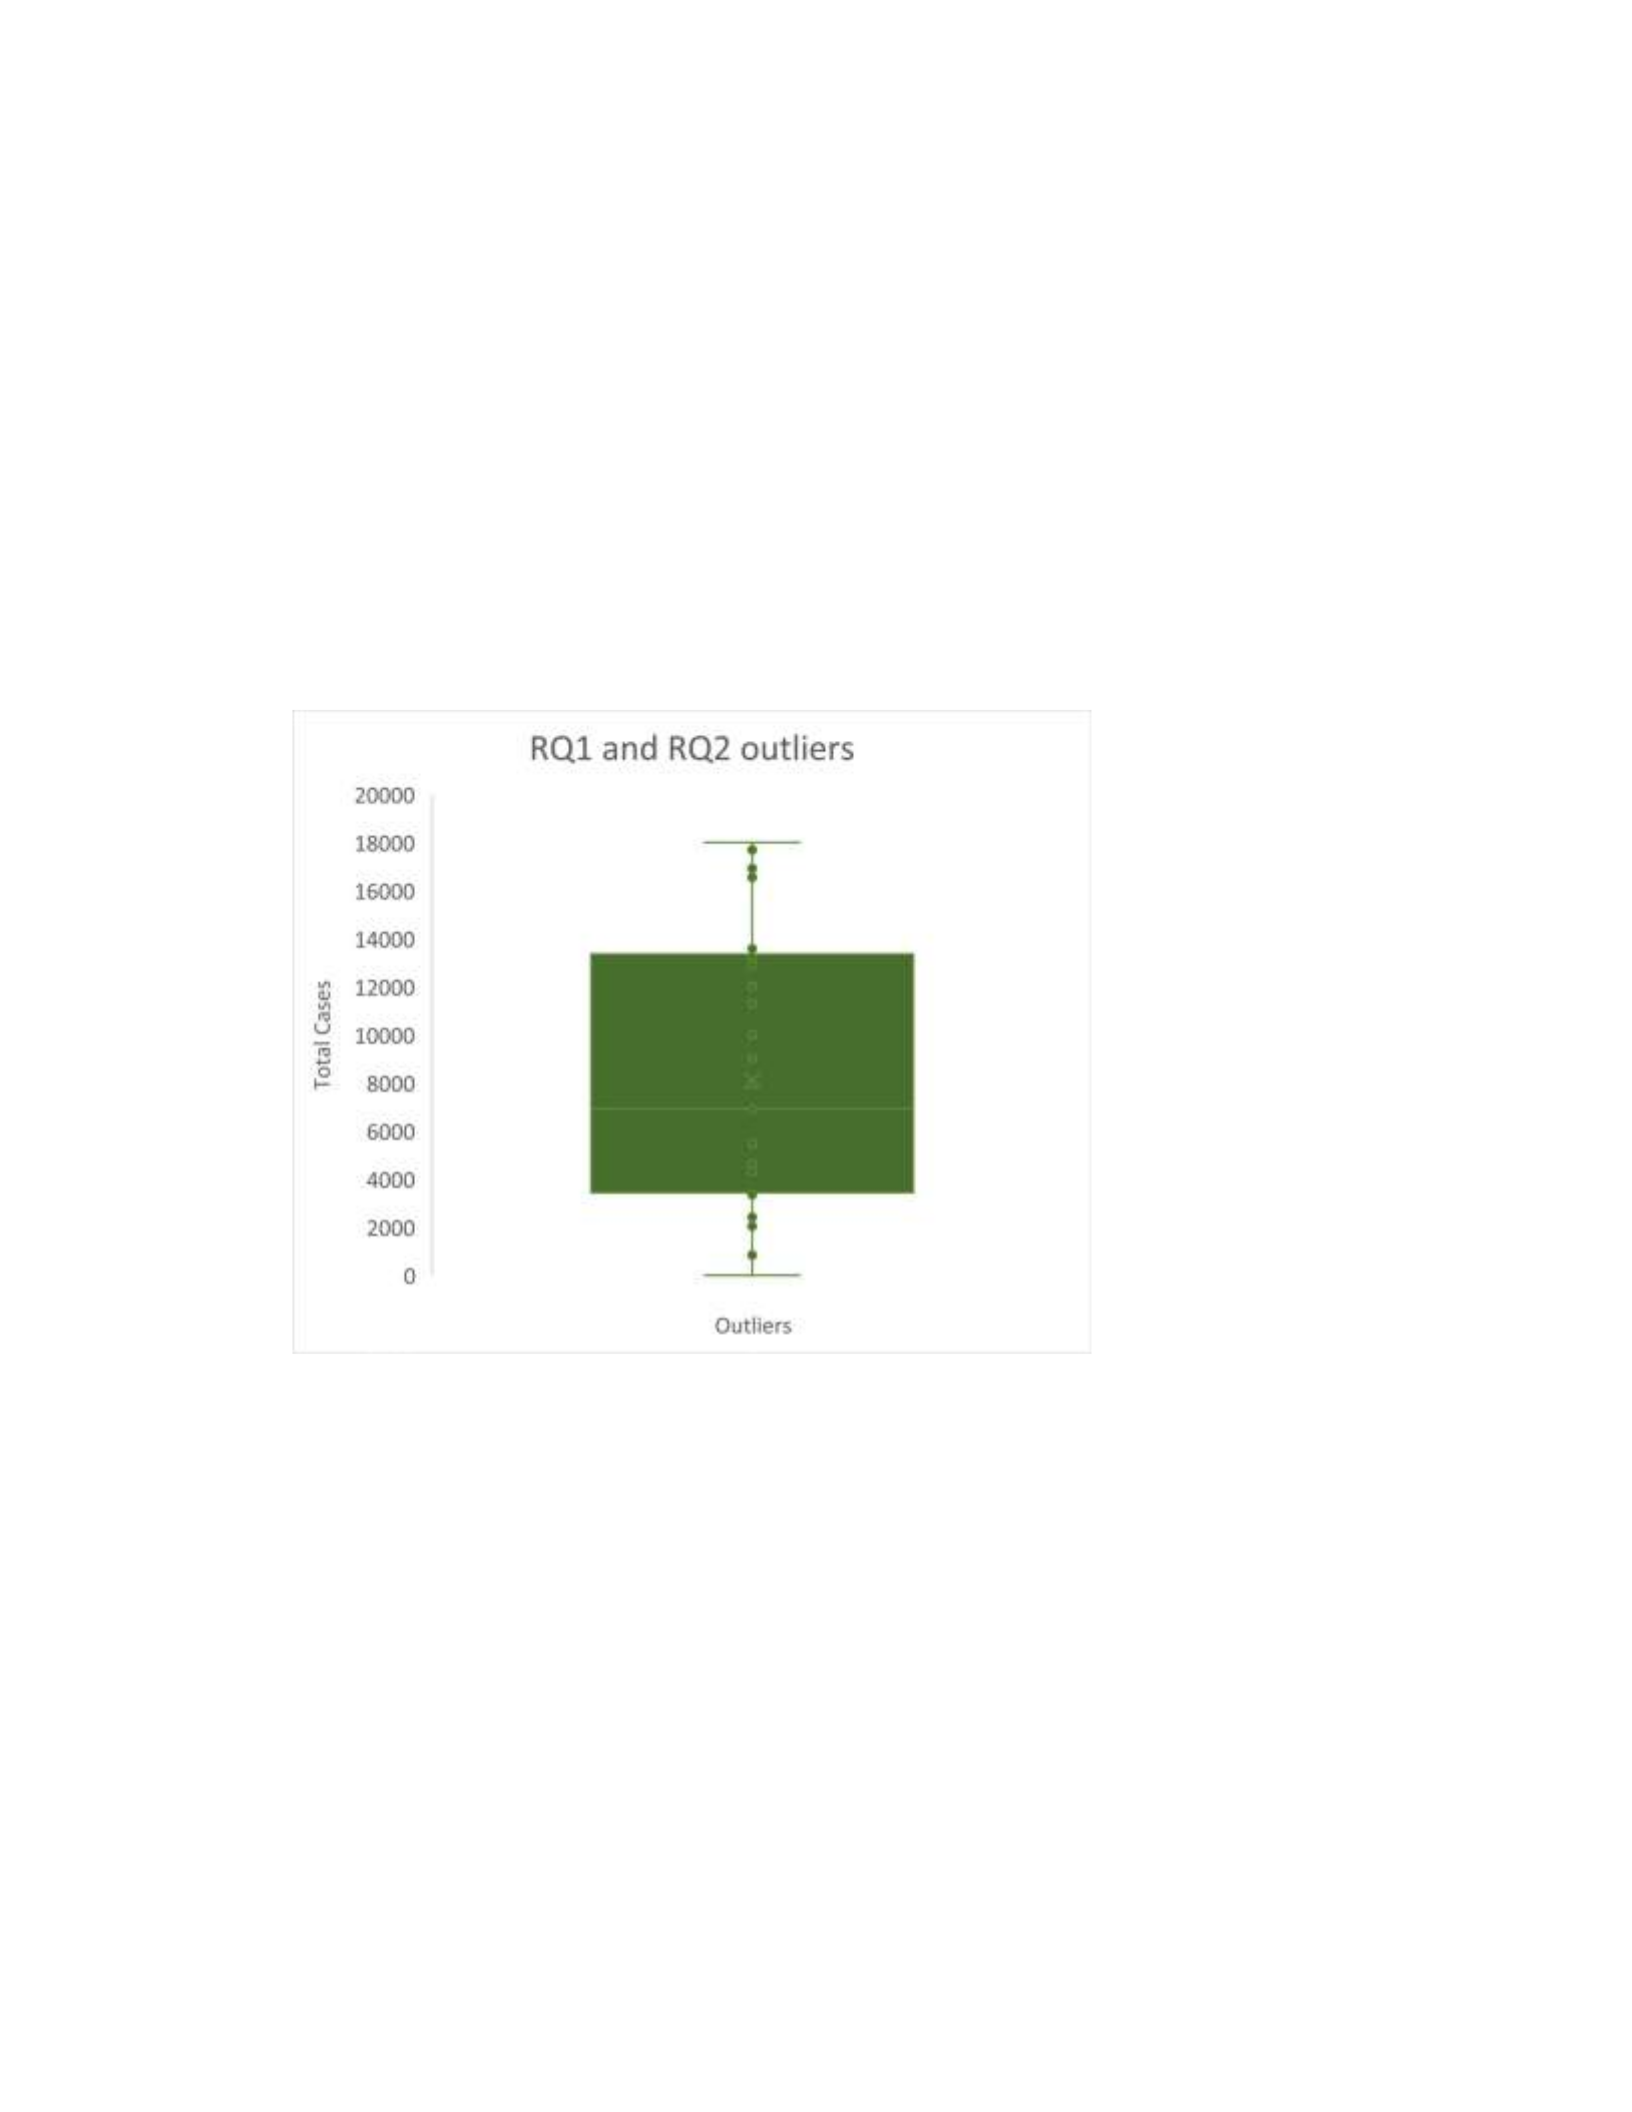
93
violated. I decided to keep the outliers. Even though outliers are sometimes
considered miscalculations (Smiti, 2020), they can aid in significant
information discovery.
Figure 4
Research Questions 1 and 2 Outliers
Figure 5
Research Question 3 Outliers

94
Statistical Analysis Findings for Research Question 1
The results are presented by RQ. Tables 1–10 noted the measurement
levels used for each study variable. RQ1 and its associated hypotheses are as
follows:
RQ1: Is there an association between location of water source, location
of toilet facility, area, wealth index, education, and sex of head of household
on child mortality in Sierra Leone?
H01: There is no association between location of water source, location
of toilet facility, area, wealth index, education, and sex of head of
household on child mortality in Sierra Leone.

95
HA1: There is an association between location of water source,
location of toilet facility, area, wealth index, education, and sex of
head of household on child mortality in Sierra Leone.
I conducted a binary logistic regression as the primary statistical
analysis to investigate RQ1. All non-responses were excluded from the
regression analysis. The results of the analysis are seen in Tables 18 and 19.
With child mortality as the independent variable and yes as the reference
category, wealth index had a statistically significant association with a p-
value of <.001, and 95% Confidence Interval (CI) between .827 and .915.
For every one unit increase of wealth, child mortality decreases by 13%.
Area also showed a statistically significant association with a p-value of
.003. It had a CI of 1.075 to 1.428. This rejects the null hypothesis for both
wealth index and area, confirming there is an association between the
mentioned variables and child mortality. The variables location of water
source, location of toilet facility, sex of head of household and education of
head of household showed no significant association between them and child
mortality (see Table 18). However, as seen in Table 19, the omnibus test of
model coefficients showed a p-value of <.001. As such the null hypothesis

96
was rejected in favor of the alternative hypothesis as there was a significant
association between the independent variables and child mortality.
Table 18
Research Question 1 Variables in the Equation
Variable B SE Wald df p Exp(B) 95% CI for
EXP(B)
LL UL
Location of the water source 6.773 2 .034
Location of the water .021 .243 .007 1 .931
1.021 source (1)
.634
1.644
Location of the water .214 .234 .835 1 .361
1.238 source (2)
.783
1.959
Location of the toilet facility .153 2 .926
Location of the toilet -.002 .086 .001 1 .981
.998 facility (1)
.843
1.181
Location of the toilet .019 .094 .042 1 .837
1.020 facility (2)
.847
1.227
Wealth index -.139 .026 29.111 1 <.001 .870
.827
.915
Sex of head of household (1) -.063 .051 1.509 1 .219 .939
.849
1.038
Area (1) .214 .072 8.753 1 .003 1.239
1.075
1.428
Education of head of .016 .020 .705 1 .401
1.017 household
.978
1.056
Constant - .259 28.099 1 <.001 .254
1.372
Note. CI = confidence interval; UL = upper limit; LL = lower limit. a
Variables entered on Step 1 were location of the water source, location

97
of the toilet facility, wealth index, sex of head of household, area, and
education of head of household.
Table 19
Research Question 1 Omnibus Tests of Model Coefficients
Step
χ2
df
p
Step 1
Step
123.483
8
<.001
Block
123.483
8
<.001
Model
123.483
8
<.001
Statistical Analysis Findings for Research Question 2
RQ2 and its corresponding hypotheses were as follows:
RQ2: Is there an association between the location of water source,
location of toilet facility and child mortality in Sierra Leone, when
controlling the factors of sex of head of household, wealth index, education,
and area?
H02: There is no association between the location of water source,
location of toilet facility and child mortality in Sierra Leone, when
controlling the factors of sex of head of household, wealth index,
education, and area.

98
HA2: There is an association between the location of water source,
location of toilet facility and child mortality in Sierra Leone, when
controlling the factors of sex of head of household, wealth index,
education, and area.
Tables 20 and 21 show the results of this regression analysis. As the
same variables as RQ1 were used, the regression analysis produced replica
results (see Table 20). The omnibus test of model coefficients produced a p-
value of <.001 (see Table 21); therefore, the null hypothesis was rejected in
lieu of the alternative hypothesis as a significant association was shown
between all variables in the regression analysis.
Table 20
Research Question 2 Variables in the Equation
Variable
B
SE Wald
df p
Exp(B) 95% CI for
EXP(B)
LL UL
Wealth index
-
.139
.026
29.111
1
<.001
.870
.827
.915
Sex of head of household (1)
-
.063
.051
1.509
1
.219
.939
.849
1.038
Area (1)
.214
.072
8.753
1
.003
1.239
1.075
1.428
Education of head of
household
.016
.020 .705
1
.401
1.017
.978
1.056
Location of the water source
6.773
2
.034

99
Location of the water source
(1)
.021
.243 .007
1
.931
1.021
.634
1.644
Location of the water source
(2)
.214
.234 .835
1
.361
1.238
.783
1.959
Location of the toilet facility
.153
2
.926
Location of the toilet facility
(1)
-
.002
.086 .001
1
.981
.998
.843
1.181
Location of the toilet facility
(2)
.019
.094 .042
1
.837
1.020
.847
1.227
Constant -1.372 .259 28.099 1 <.001
.254
Note. CI = confidence interval; UL = upper limit; LL = lower limit.
a Variables entered on Step 0 were wealth index, sex of head of
household, area, and education of head of household.
b Variables entered on Step 1 were location of the water source and
location of the toilet facility.
Table 21
Research Question 2 Omnibus Tests of Model Coefficients
Step
χ2
df
p
Step 1
Step
7.624
4
.106
Block
7.624
4
.106
Model
123.483
8
<.001

100
Statistical Analysis Findings for Research Question 3
RQ3 and its associated hypotheses were as follows:
RQ3: Is there an association between water treatment type, number of
households using toilet facility and child mortality in Sierra Leone, when
controlling the factors of sex of head of household, wealth index, education,
and area?
H03: There is no association between water treatment type, number of
households using toilet facility and child mortality in Sierra Leone,
when controlling the factors of sex of head of household, wealth
index, education, and area.
HA3: There is an association between water treatment type, number of
households using toilet facility, and child mortality in Sierra Leone,
when controlling the factors of sex of head of household, wealth
index, education, and area.
Tables 22 and 23 show the results of this regression analysis. The
recoded water treatment method and households using toilet variables were
used as independent variables. The variables of area, wealth index, education
and sex of head of household were again used as control variables. The
independent variables showed no statistically significant association; water

101
treatment method had a p-value of .068 and households using toilet had a p-
value of .079 (see Table 22). However, the omnibus test of model coefficients
produced a p-value of <.001 (see Table 23). This result supported a rejection
of the null hypothesis because a significant association was shown between
the independent and control variables and the dependent variable of child
mortality.

102
Table 22
Research Question 3 Variables in the Equation
Variable B SE Wald df p Exp(B) 95% CI for EXP(B)
LL UL
Wealth index
.142
.031
20.985
1 <.001
1.152 1.084
1.224
Sex of head of
household(1)
.132
.062
4.470
1
.034
1.141 1.010
1.290
Area(1)
-.230
.085
7.280
1
.007
.794
.672
.939
Education of
head of
household
-.004
.023
.026
1
.871
.996
.952
1.043
Water treatment
method
.132
.076
3.055
1
.080
1.141
.984
1.324
Households using
toilet facility
12.423
9
.190
Households
using toilet
facility(1)
-.103
.090
1.306
1
.253
.902
.756
1.076
Households
using toilet
facility(2)
-.095
.096
.966
1
.326
.910
.753
1.099
Households
using toilet
facility(3)
-.067
.108
.387
1
.534
.935
.757
1.155
Households
using toilet
facility(4)
.033
.129
.064
1
.800
1.033
.803
1.330
Households
using toilet
facility(5)
-.215
.132
2.642
1
.104
.806
.622
1.045
Households
using toilet
facility(6)
-.297
.166
3.194
1
.074
.743
.537
1.029
Households
using toilet
facility(7)
.193
.268
.520
1
.471
1.213
.718
2.050
103
Households
using toilet
facility(8)
-.240
.107
5.043
1
.025
.787
.638
.970
Households
using toilet
facility(9)
-.415
.250
2.753
1
.097
.660
.404
1.078
Constant
1.162
.149
60.940
1 <.001
3.196
Note. CI = confidence interval; UL = upper limit; LL = lower limit. a
Variables entered on Step 0 were wealth index, sex of head of
household, area, and education of head of household.
b Variables entered on Step 1 were water treatment method and households
using toilet
facility.
Table 23
Research Question 3 Omnibus Tests of Model Coefficients
Step 1
Step
6.518
2
.038
Block
6.518
2
.038
Model
96.311
6
<.001
Summary
In this section, I analyzed the association between WASH
demographic variables against the dependent variable, child mortality. The
first RQ analyzed the impact of location of water source, location of toilet
Step
χ
2
df
p

104
facility, area, wealth index, education, and sex of head of household on child
mortality in Sierra Leone. The second RQ looked at the impact of both
location of water source and toilet facility on child mortality when
controlling for the demographic factors mentioned in the first RQ. The third
RQ analyzed water treatment type and number of households using a single
toilet facility and their impact on child mortality. A binary logistic regression
was conducted for all RQs. Significant statistical findings in the RQ1
suggests a relationship between the question variables, specifically between
area and wealth index on child mortality in Sierra Leone.
The other independent variables mentioned in the RQ did not show
significant statistical associations, nor did the independent variables from the
following questions. Section 4 will include an introduction, interpretation of
the findings, specifically as it relates to the SEM framework chosen for this
study. Limitations of the study, recommendations for future research, and
social change implications are be discussed.

105
Section 4: Application to Professional Practice and Implications for Social
Change
Introduction
The purpose of this quantitative cross-sectional study was to examine
the impact of WASH variables on child mortality. Secondary data was
retrieved from the 2017 MICS6 to answer the RQs. Three questions were
assessed in the study: Is there an association between location of water
source, location of toilet facility, area, wealth index, education, and sex of
head of household on child mortality in Sierra Leone?; Is there an association
between the location of water source, location of toilet facility and child
mortality in Sierra Leone, when controlling the factors of sex of head of
household, wealth index, education, and area?; Is there an association
between water treatment type, number of households using toilet facility and
child mortality in Sierra Leone, when controlling the factors of sex of head of
household, wealth index, education, and area? Key findings included that
none of the WASH related variables had a statistically significant association
however, when looking at the omnibus test of model coefficients, all
questions showed signs of statistical significance. Looking at each variable
individually, for question one and two, a statistically significant association

106
was found for both area and wealth index with regard to child mortality. RQ3
showed a significance with the wealth index variable as well.
Interpretation of the Findings
RQ1 examined the relationship between location of water source,
location of toilet facility, area, wealth index, education, and sex of head of
household on child mortality, determining statistically significant
associations between area, p= .003, CI (1.075, 1.428) and wealth, p= <.001,
CI (.827, .915). The other independent variables, location of water source, p=
.034, location of toilet facility, p= .926, sex of head of household, p= .219
and education of head of household, p= .401, showed no statical significance
on child mortality. However, the omnibus test of model coefficients had a
pvalue of <.001, showing statistical significance. RQ2 examined the
relationship between location of water source, location of toilet facility and
child mortality while controlling the factors area, wealth index, sex of head
of household and education. The results of the analysis matched those of
RQ1. Similarly to question three, no statistically significance was found
between water treatment type, p=.068, CI (.751, 1.010) or households using
toilet, p=.079, CI (.999, 1.009) while the wealth index variable did show a
statistically significant association, p= <.001, CI (.816, .921) and was used as

107
a control variable for the question. The RQ did however show statistical
significance uniformly with an omnibus test of model coefficients p-value of
<.001.
The Socioecological Model as a Lens for Interpreting the Findings
Urie Bronfenbrenner’s SEM theoretical framework focuses on health
outcomes are impacted by the characteristics of the individual, community,
the environment, and public policy (Bronfenbrenner, 1979; Kilanowski,
2017; Salihu et al., 2015; Scarneo et al., 2019). The analysis of RQs in this
study using this framework was appropriate for determining how the
variables of this study fit into the categories described by Bronfenbrenner. As
the study RQs were determined to show statistical significance, specifically
the area and wealth index variables, the aspects of the SEM can be further
analyzed.
Child mortality outcomes are heavily influenced by socioeconomic
and demographic factors (Zewudie et al., 2020). The authors analysis
determined that within the wealth index category, children from families that
fell in the poor economic status category (6.8%), were more likely to die than
those in the middle (5.14%) or rich (4,74%) economic status category. They
also reported higher mortality rates in rural (6.55%) versus urban areas

108
(3.39%). These findings validate the statistical significance seen with both
the wealth index and area variables in the RQs. Asif et al.’s (2022) study in
Pakistan also looked at demographic and socioeconomic variables related to
WASH, determining women’s education, husband’s education, the wealth
status of their households, access to clean drinking water, access to toilet
facilities, and exposure to mass media all impacted child mortality. In fact,
household wealth status weakens the association between women’s education
and child mortality. This study produced similar results with similar
variables, sharing insights on this studies limitations, future
recommendations, and social change implications.
Limitations of the Study
There were a few limitations in this secondary data analysis worth
recognizing relative to the research objectives. The first limitation was the
age of the data. While it was the most recent MICS data available for Sierra
Leone, it was collected in 2017. Health and water conditions may have
changed since then and that was not accounted for with this data. The second
limitation was the generalizability of the study; the study was limited to the
four WASH-related variables used, lowering its applicability as there were
other variables that could have been used as well. There was also the

109
understanding of these variables; the MICS6 was UNICEFs first attempt at
water-quality testing so some kinks may need to be worked out as they
prepare for the MICS7. Other limitations of the study included the
responsiveness of participants and the variable classifications. All the
variables used for this study were also categorical. Brown et al. (2024)
asserted that studies open themselves up to misclassification when one or
more categorical variables are mismeasured or misreported. While the
overall sample size for the data set was 18,006, the water treatment variable
had a response rate of 9.6%, this response rate was not enough to make a
statistical inference on the impact of water treatment type on child mortality.
This is true for other variables in the study as well. Of all the variables used
for this study, area and wealth index had the least amount of missing
participant data. The amount of missing data could have impacted several
aspects of the data from the normality to the level of collinearity seen.
The area of study was also specific to Sierra Leone, making it difficult
to generalize for other parts of sub-Saharan Africa. The understanding of
participants could have been different in this region compared to others.
Aspects of water source and toilet facility locality could be different from

110
one country to the next or even when looking more microscopically, between
provinces in Sierra Leone.
As this was a quantitative secondary analysis study, it did limit the
level of engagement, potentially opening the study up to biases. According to
Brown et al. (2024), biased studies can mislead, and negatively impact both
public health and clinical practices. A qualitative or mixed-methods approach
would have required different techniques as the possibility of receiving
participant perspectives and asking in-depth questions could have provided
valuable information that could improve any study.
Recommendations for Further Research
The study did not necessarily provide the expected results when
looking at variables related to WASH but there were some key takeaways.
Sierra Leone is one of the most underdeveloped countries in the world and
access to health care is limited by geographical barriers (Caviglia et al.,
2021). Social and structural factors play a critical role in driving child health
outcomes. With area and wealth index being the factors of most influence, it
is important to work towards decreasing those barriers. Sierra Leone is
working and will need to continue to work towards universal health care. As
one of two African countries to pilot the Universal Health Preparedness

111
Review (WHO, 2023), Sierra Leone has begun the process of trying to
reduce both the area and wealth index gap.
This study should be conducted again with the MICS7 when it is
released. The hope is to see better participant activity that will aid in getting
a more statistically significant response and using recent data. For this study,
that also includes altering either RQs 1 or 2 so that they produce different
results if the study were to be done using a binary logistic regression again.
This study can also be replicated using Sierra Leone DHS data. The most
recent DHS data is from 2019 and may have a more complete data set than
what was provided by UNICEFs MICS data.
Including more variables will also increase the generalizability of the
study and increase the scope. Due to the limitations of the scope and
questions one and two having the same variables and results, there were
restriction limits on the issues that could be examined. Including province
data could further aid in determining what parts of Sierra Leone need
interventions more than others. This study determined a significant
association between area and wealth index which were the variables that had
the most complete responses. Looking at data at the providence level can aid
in determining where interventions are needed most. Additional training is

112
also needed to ensure data collectors are confirming that participants are
completing questionnaires in their entirety without coercing them on what to
select. The thought behind this recommendation is the reported results, which
showed many missing responses for key study variables.
Public Health Practice and Field-Based Products
Child mortality is an indicator of child health, the quality of life of a
population and overall country development (Zewudie et al., 2020). Despite
improvements in disease prevention and child mortality over the last few
decades, health disparities still exist in socioeconomic, ethnicity and sex/
gender (Harari and Lee, 2021). Policy interventions geared specifically
towards socioeconomic advances decreasing the gap between wealth groups
are needed as wealth was shown to statistically impact child mortality in this
study. While the WASH, sex, and education variables showed no statistical
significance on child mortality, the need for education programs still exists.
Thomson et al. (2018) discussed government measures seen in high-income
countries and the impact they have made. They discussed public health and
social policies to include cash transfers, housing, education, and health care
services. These programs have been said to alleviate health effects linked
with socioeconomic inequalities. Research has shown that countries with

113
provisions surrounding alleviating the wealth gap have better population
health than those without these policies in place.
Lagakos (2020) discusses how a divide between urban and rural
communities is ever present and measured by income, consumption, and
other factors. Even the United States sees urban–rural disparities with respect
to public health (Leider, 2020). Both authors discussed how low-income
rural areas mortality rates decreased slower than lowincome urban areas.
With similar patterns of urban–rural disparities being seen in high income
countries, some of what has been done to decrease these differences can be
translated to low-income countries. Targeting rural communities with
government funding can aid in lessening the area disparities currently seen.
Positive Social Change
The results of this study may contribute to improved child mortality
prevention and management programs by the government and local health
officials. The findings of this study can positively contribute to social change
intended to reduce the burden of child mortality in Sierra Leone and other
developing countries in sub-Saharan Africa. Reducing child mortality is a
positive social change that will aid Sierra Leone in improving life expectancy
for all.

114
Conclusion
Child mortality has often been used as a population health indicator for
a given community (Gonzalez & Gilleskie, 2017). As such, monitoring
health outcomes has been essential in identifying priorities in public health
planning and improvement initiatives (Jorda et al., 2024). The purpose of this
quantitative study was to examine the role of WASH on child mortality in
Sierra Leone. Demographic variables were added as this study was looked at
through the SEM lens. This proved to be insightful as demographic variable
bore more statistical significance than WASH variables as wealth index and
area both had p-values of <.005 for questions one and two. The findings from
this study demonstrate the importance of government programs aimed at
decreasing the wealth index gap and creating opportunities in rural areas that
were not previously available. With time and continued resources, the impact
these demographics have on child mortality can one day be minimal.
115
References
Abrams, A. L., Carden, K., Teta, C., & Wågsæther, K. (2021). Water,
sanitation, and hygiene vulnerability among rural areas and small
towns in South Africa:
Exploring the role of climate change, marginalization, and inequality.
Water,
13(20), Article 2810. https://doi.org/10.3390/w13202810
Abubakar, I. R. (2019). Factors influencing household access to drinking
water in
Nigeria. Utilities Policy, 58, 40–51.
https://doi.org/10.1016/j.jup.2019.03.005
Ademas, A., Adane, M., Keleb, A., Berihun, G., & Tesfaw, G. (2021). Water,
sanitation, and hygiene as a priority intervention for stunting in under-
five children in northwest Ethiopia: A community-based cross-
sectional study. Italian Journal of
Pediatrics, 47, Article 174. https://doi.org/10.1186/s13052-021-01128-
y
Aemiro, M. T., & Getachew, Y. (2022). Sustainability of one WASH facilities
in the rural settings of north Shoa zone, Amhara region, north east
Ethiopia, 2020.
Journal of Nutrition and Metabolism, 2022, Article 1711389.

116
https://doi.org/10.1155/2022/1711389
Agency for Toxic Substances and Diseases Registry. (2015, June 25).
Chapter 1: Models and Frameworks | Principles of Community
Engagement | ATSDR. Centers for
Disease Control and Prevention.
https://www.atsdr.cdc.gov/communityengagement/pce_models.html
Aleixo, B., Pena, J. L., Heller, L., & Rezende, S. (2019). Infrastructure is a
necessary but insufficient condition to eliminate inequalities in access
to water: Research of a rural community intervention in Northeast
Brazil. Science of the Total
Environment, 652, 1445–1455.
https://doi.org/10.1016/j.scitotenv.2018.10.202
Allwell-Brown, G., Hussain-Alkhateeb, L., Sewe, M. O., Kitutu, F. E.,
Strömdahl, S., Mårtensson, A., & Johansson, E. W. (2021).
Determinants of trends in reported antibiotic use among sick children
under five years of age across low-income and middle-income
countries in 2005–17: A systematic analysis of user characteristics
based on 132 national surveys from 73 countries. International
Journal of

117
Infectious Diseases, 108, 473–482.
https://doi.org/10.1016/j.ijid.2021.05.058
Amegbor, P. M., & Addae, A. (2023). Spatiotemporal analysis of the effect of
global development indicators on child mortality. International
Journal of Health
Geographics, 22, Article 9. https://doi.org/10.1186/s12942-023-00330-
x
Andrade, C. (2020). Sample size and its importance in research. Indian
Journal of
Psychological Medicine, 42(1), 102–103.
https://doi.org/10.4103/IJPSYM.IJPSYM_504_19
Anyamele, O. D. (2020). Disparities and inequality in infant and child
mortality among the 36 states and federal capital territory (FCT,
Abuja), Nigeria. Journal of Health
Care for the Poor and Underserved, 31(3), 1166–1190.
https://doi.org/10.1353/hpu.2020.0088
Asif, M. F., Pervaiz, Z., Afridi, J. R., Safdar, R., Abid, G., & Lassi, Z. S.
(2022). Socioeconomic determinants of child mortality in Pakistan and
the moderating role of household’s wealth index. BMC Pediatrics, 22,
Article 3.
https://doi.org/10.1186/s12887-021-03076-2
118
Bain, R., Johnston, R., Khan, S., Hancioglu, A., & Slaymaker, T. (2021).
Monitoring drinking water quality in nationally representative household
surveys in low- and middle-income countries: Cross-sectional analysis of 27
Multiple Indicator
Cluster Surveys 2014–2020. Environmental Health Perspectives,
129(9), Article
097010. https://doi.org/10.1289/ehp8459
Bainter, S. A., & Curran, P. J. (2015). Advantages of integrative data analysis
for developmental research. Journal of Cognition and Development,
16(1), 1–10.
https://doi.org/10.1080/15248372.2013.871721
Balaj, M., York, H. W., Sripada, K., Besnier, E., Vonen, H. D., Aravkin, A.,
Friedman, J.,
Griswold, M., Jensen, M. R., Mohammad, T., Mullany, E. C., Solhaug,
S.,
Sorensen, R., Stonkute, D., Tallaksen, A., Whisnant, J., Zheng, P.,
Gakidou, E., & Eikemo, T. A. (2021). Parental education and
inequalities in child mortality: A global systematic review and meta-
analysis. The Lancet, 398(10300), 608–620.
https://doi.org/10.1016/S0140-6736(21)00534-1
119
Bayu, T., Kim, H., & Oki, T. (2020). Water governance contribution to water
and sanitation access equality in developing countries. Water
Resources Research,
56(4), Article e2019WR025330.
https://doi.org/10.1029/2019wr025330
Beatriz, E. D., Molnar, B. E., Griffith, J. L., & Salhi, C. (2018). Urban-rural
disparity and urban population growth: A multilevel analysis of under-
5 mortality in 30 sub-
Saharan African countries. Health & Place, 52, 196–204.
https://doi.org/10.1016/j.healthplace.2018.06.006
Berhe, A. A., Aregay, A. D., Abreha, A. A., Aregay, A. B., Gebretsadik, A.
W., Negash,
D. Z., Gebreegziabher, E. G., Demoz, K. G., Fenta, K. A., & Mamo,
N. B. (2020).
Knowledge, attitude, and practices on water, sanitation, and hygiene
among rural residents in Tigray region, Northern Ethiopia. Journal of
Environmental and
Public Health, 2020, Article 5460168.
https://doi.org/10.1155/2020/5460168
Bhusal, M. K., & Khanal, S. P. (2022). A systematic review of factors
associated with under-five child mortality. BioMed Research
International, 2022, 1–19. Article

120
1181409. https://doi.org/10.1155/2022/1181409
Bishoge, O. K. (2021). Challenges facing sustainable water supply, sanitation
and hygiene achievement in urban areas in sub-Saharan Africa. Local
Environment,
26(7), 1–15. https://doi.org/10.1080/13549839.2021.1931074
Bisung, E., & Dickin, S. (2019). Concept mapping: Engaging stakeholders to
identify factors that contribute to empowerment in the water and
sanitation sector in West
Africa. SSM - Population Health, 9, Article 100490.
https://doi.org/10.1016/j.ssmph.2019.100490
Bizzego, A., Gabrieli, G., Bornstein, M. H., Deater-Deckard, K., Lansford, J.
E., Bradley, R. H., Costa, M., & Esposito, G. (2021). Predictors of
contemporary under-5 child mortality in low- and middle-income
countries: A machine learning approach. International Journal of
Environmental Research and Public Health, 18(3), 1315.
https://doi.org/10.3390/ijerph18031315
Boateng, E. Y., & Abaye, D. A. (2019). A review of the logistic regression
model with emphasis on medical research. Journal of Data Analysis
and Information

121
Processing, 07(04), 190–207. https://doi.org/10.4236/jdaip.2019.74012
Bobbitt, Z. (2021, January 21). The Durbin-Watson test: Definition &
example.
Statology. https://www.statology.org/durbin-watson-test/
Bronfenbrenner, U. (1979). The ecology of human development: Experiments
by nature and design. Harvard University Press.
Brown, J. P., Hunnicutt, J. N., Ali, M. S., Bhaskaran, K., Cole, A., Langan, S.
M., Nitsch, D., Rentsch, C. T., Galwey, N. W., Wing, K., & Douglas, I.
J. (2024).
Quantifying possible bias in clinical and epidemiological studies with
quantitative bias analysis: Common approaches and limitations. BMJ,
385, e076365.
https://doi.org/10.1136/bmj-2023-076365
Calderón-Villarreal, A., Schweitzer, R., & Kayser, G. (2022). Social and
geographic inequalities in water, sanitation and hygiene access in 21
refugee camps and settlements in Bangladesh, Kenya, Uganda, South
Sudan, and Zimbabwe.
International Journal for Equity in Health, 21(1), Article 27.
https://doi.org/10.1186/s12939-022-01626-3

122
Caperon, L., Saville, F., & Ahern, S. (2022). Developing a socio-ecological
model for community engagement in a health programme in an
underserved urban area.
PLOS ONE, 17(9), Article e0275092.
https://doi.org/10.1371/journal.pone.0275092
Carshon-Marsh, R., Aimone, A., Ansumana, R., Swaray, I. B., Assalif, A.,
Musa, A., Meh, C., Smart, F., Fu, S. H., Newcombe, L., Kamadod, R.,
Saikia, N., Gelband,
H., Jambai, A., & Jha, P. (2022). Child, maternal, and adult mortality
in Sierra
Leone: nationally representative mortality survey 2018–20. The Lancet
Global Health, 10(1), e114–e123. https://doi.org/10.1016/S2214-
109X(21)00459-9 Caviglia, M., Dell’Aringa, M., Putoto, G., Buson,
R., Pini, S., Youkee, D., Jambai, A.,
Vandy, M. J., Rosi, P., Hubloue, I., Della Corte, F., Ragazzoni, L., &
BaroneAdesi, F. (2021). Improving access to healthcare in Sierra
Leone: The role of the newly developed national emergency medical
service. International Journal of
Environmental Research and Public Health, 18(18), Article 9546.

123
https://doi.org/10.3390/ijerph18189546
Centers for Disease Control and Prevention. (n.d.-a). Sanitation & hygiene
home. Centers for Disease Control and Prevention.
https://www.cdc.gov/healthywater/global/sanitation/index.html
Centers for Disease Control and Prevention. (n.d.-b). The social-ecological
model: A framework for prevention. Centers for Disease Control and
Prevention; CDC.
https://www.cdc.gov/violenceprevention/about/social-
ecologicalmodel.html
Centers for Disease Control and Prevention. (n.d.-c). Water, sanitation, and
environmentally related hygiene . Www.cdc.gov.
https://www.cdc.gov/hygiene/index.html
Chancellor’s Doctoral Incentive Program. (n.d.). Quantitative research. The
California
State University
https://cdip.merlot.org/facultyresearch/QuanitativeResearch.html
Chaudhuri, S., & Roy, M. (2017). Rural-urban spatial inequality in water and
sanitation facilities in India: A cross-sectional study from household to
national level.
Applied Geography, 85, 27–38.
https://doi.org/10.1016/j.apgeog.2017.05.003
124
Chazan, B. (2021). Principles and pedagogies in Jewish education (pp. 13–
21). Springer
Nature.
Chen, S.-W., Keglovits, M., Devine, M., & Stark, S. (2022).
Sociodemographic differences in respondent preferences for survey
formats: Sampling bias and potential threats to external validity.
Archives of Rehabilitation Research and
Clinical Translation, 4(1), Article 100175.
https://doi.org/10.1016/j.arrct.2021.100175
Chen, X., Orom, H., Hay, J. L., Waters, E. A., Schofield, E., Li, Y., &
Kiviniemi, M. T.
(2018). Differences in rural and urban health information access and
use. The
Journal of Rural Health, 35(3), 405–417.
https://doi.org/10.1111/jrh.12335
Chirgwin, H., Cairncross, S., Zehra, D., & Sharma Waddington, H. (2021).
Interventions promoting uptake of water, sanitation and hygiene
(WASH) technologies in low‐ and middle‐income countries: An
evidence and gap map of effectiveness studies.
Campbell Systematic Reviews, 17(4). https://doi.org/10.1002/cl2.1194
Chivardi, C., Zamudio Sosa, A., Medeiros Cavalcanti, D., Alejandro
Ordoñez, J., Felipe
125
Diaz, J., Zuluaga, D., Almeida, C., Serván-Mori, E., Hessel, P.,
Moncayo, A. L.,
& Rasella, D. (2023). Understanding the social determinants of child
mortality in
Latin America over the last two decades: A machine learning
approach. Research
Square (Research Square). https://doi.org/10.21203/rs.3.rs-2913723/v1
Cobbinah, P. B., Kosoe, E. A., & Diawuo, F. (2020). Environmental planning
crisis in urban Ghana: Local responses to nature’s call. Science of the
Total Environment,
701, Article 134898. https://doi.org/10.1016/j.scitotenv.2019.134898
Cumming, O., Arnold, B. F., Ban, R., Clasen, T., Esteves Mills, J., Freeman,
M. C.,
Gordon, B., Guiteras, R., Howard, G., Hunter, P. R., Johnston, R. B.,
Pickering,
A. J., Prendergast, A. J., Prüss-Ustün, A., Rosenboom, J. W., Spears,
D., Sundberg, S., Wolf, J., Null, C., & Luby, S. P. (2019). The
implications of three major new trials for the effect of water, sanitation
and hygiene on childhood diarrhea and stunting: A consensus
statement. BMC Medicine, 17(1).
https://doi.org/10.1186/s12916-019-1410-x

126
Daly, S. W., Lowe, J., Hornsby, G. M., & Harris, A. R. (2021). Multiple
water source use in low- and middle-income countries: A systematic
review. Journal of Water and
Health, 19(3), 370–392. https://doi.org/10.2166/wh.2021.205
Das, A. (2021). Logistic regression. In: Maggino, F. (Eds) Encyclopedia of
Quality of
Life and Well-Being Research. Springer, Cham, 1–2.
https://doi.org/10.1007/978-
3-319-69909-7_1689-2
The Demographic and Health Surveys Program. (n.d.). The DHS program -
research topics - wealth index. Dhsprogram.com.
https://dhsprogram.com/topics/wealthindex/
Dery, F., Bisung, E., Dickin, S., & Dyer, M. (2019). Understanding
empowerment in water, sanitation, and hygiene (WASH): a scoping
review. Journal of Water,
Sanitation and Hygiene for Development, 10(1), 5–15.
https://doi.org/10.2166/washdev.2019.077
Dey, N. C., Parvez, M., Islam, M. R., Mistry, S. K., & Levine, D. I. (2019).
Effectiveness of a community-based water, sanitation, and hygiene
(WASH) intervention in reduction of diarrhoea among under-five
127
children: Evidence from a repeated cross-sectional study (2007–2015)
in rural Bangladesh. International Journal of
Hygiene and Environmental Health, 222(8), 1098–1108.
https://doi.org/10.1016/j.ijheh.2019.08.006
Dickin, S., Bisung, E., Nansi, J., & Charles, K. (2021). Empowerment in
water, sanitation and hygiene index. World Development, 137, 105158.
https://doi.org/10.1016/j.worlddev.2020.105158
Economic and Social Commission for Western Asia. (n.d.). Head of
household. United
Nations Economic and Social Commission for Western Asia.
https://www.unescwa.org/sd-glossary/head-household-0
Ekholuenetale, M., Wegbom, A. I., Tudeme, G., & Onikan, A. (2020).
Household factors associated with infant and under-five mortality in
sub-Saharan Africa countries.
International Journal of Child Care and Education Policy, 14(1).
https://doi.org/10.1186/s40723-020-00075-1
Ezbakhe, F., Giné-Garriga, R., & Pérez-Foguet, A. (2019). Leaving no one
behind: Evaluating access to water, sanitation and hygiene for
vulnerable and marginalized groups. Science of the Total Environment,
683, 537–546. https://doi.org/10.1016/j.scitotenv.2019.05.207
128
Ezbakhe, F., & Pérez Foguet, A. (2020). Child mortality levels and trends: A
new compositional approach. Demographic Research, 43, 1263–1296.
https://doi.org/10.4054/demres.2020.43.43
Fagbamigbe, A. F., Adebola, O. G., Dukhi, N., Fagbamigbe, O. S., &
Uthman, O. A. (2021). Exploring the socio-economic determinants of
educational inequalities in diarrhoea among under-five children in
low- and middle-income countries: A
Fairlie decomposition analysis. Archives of Public Health, 79(1).
https://doi.org/10.1186/s13690-021-00639-8
Ferreira, D. C., Graziele, I., Marques, R. C., & Gonçalves, J. (2021).
Investment in drinking water and sanitation infrastructure and its
impact on waterborne diseases dissemination: The Brazilian case.
Science of the Total Environment, 779, Article
146279. https://doi.org/10.1016/j.scitotenv.2021.146279
Gaffan, N., Kpozehouen, A., Dégbey, C., Ahanhanzo, Y. G., & Paraïso, M. N.
(2023). Effects of household access to water, sanitation, and hygiene
services on underfive mortality in Sub-Saharan Africa. 11.
https://doi.org/10.3389/fpubh.2023.1136299
129
Gebremichael, S. G., Yismaw, E., Tsegaw, B. D., & Shibeshi, A. D. (2021).
Determinants of water source use, quality of water, sanitation and
hygiene perceptions among urban households in North-West Ethiopia:
A cross-sectional study. PLoS ONE, 16(4), Article e0239502.
https://doi.org/10.1371/journal.pone.0239502
Girma, M., Hussein, A., Norris, T., Genye, T., Tessema, M., Bossuyt, A.,
Hadis, M., Zyl,
C., Goyol, K., & Samuel, A. (2021). Progress in water, sanitation and
hygiene (WASH) coverage and potential contribution to the decline in
diarrhea and stunting in Ethiopia. Maternal & Child Nutrition.
https://doi.org/10.1111/mcn.13280
Gonzalez, R. M., & Gilleskie, D. (2017). Infant mortality rate as a measure
of a country’s health: A robust method to improve reliability and
comparability. Demography,
54(2), 701–720. https://doi.org/10.1007/s13524-017-0553-7
Habtegiorgis, Y., Sisay, T., Kloos, H., Malede, A., Yalew, M., Arefaynie, M.,
Damtie,
Y., Kefale, B., Tegegne, T. B., Addisu, E., Lingerew, M., Berhanu, L.,
Berihun,
G., Natnael, T., Abebe, M., Feleke, A., Gizeyatu, A., Ademas, A.,
Fentaw, Z., & Yayeh, T. M. (2021). Menstrual hygiene practices
130
among high school girls in urban areas in Northeastern Ethiopia: A
neglected issue in water, sanitation, and hygiene research. PLOS ONE,
16(6), Article e0248825.
https://doi.org/10.1371/journal.pone.0248825
Haque, S. S., & Freeman, M. C. (2021). The applications of implementation
science in water, sanitation, and hygiene (WASH) research and
practice. Environmental
Health Perspectives, 129(6), Article 065002.
https://doi.org/10.1289/ehp7762
Harari, L., & Lee, C. (2021). Intersectionality in quantitative health
disparities research: A systematic review of challenges and limitations
in empirical studies. Social
Science & Medicine, 277, Article 113876.
https://doi.org/10.1016/j.socscimed.2021.113876
Harris, J. K. (2021). Primer on binary logistic regression. Family Medicine
and
Community Health, 9(Suppl 1), Article e001290.
https://doi.org/10.1136/fmch-
2021-001290
Harrison, B. L., Ogara, C., Gladstone, M., Carrol, E. D., Dusabe-Richards, J.,
MedinaLara, A., Ditai, J., & Weeks, A. D. (2019). “We have to clean
131
ourselves to ensure that our children are healthy and beautiful”:
Findings from a qualitative assessment of a hand hygiene poster in
rural Uganda. BMC Public Health, 19(1).
https://doi.org/10.1186/s12889-018-6343-3
Headey, D., & Palloni, G. (2019). Water, sanitation, and child health:
Evidence from subnational panel data in 59 countries. Demography,
56(2), 729–752.
https://doi.org/10.1007/s13524-019-00760-y
Hosking, R., O’Connor, S. Y., Wangdi, K., Kurscheid, J., & Lal, A. (2022).
Acceptability measures of water, sanitation and hygiene interventions
in low- and middleincome countries, a systematic review. PLOS
Neglected Tropical Diseases, 16(9),
Article e0010702. https://doi.org/10.1371/journal.pntd.0010702
Ingutia, R., Rezitis, A. N., & Sumelius, J. (2020). Child poverty, status of
rural women and education in sub Saharan Africa. Children and Youth
Services Review, 111,
Article 104869. https://doi.org/10.1016/j.childyouth.2020.104869
Jacobs, C., Musukuma, M., Sikapande, B., Chooye, O., Wehrmeister, F. C.,
Boerma, T., Michelo, C., & Blanchard, A. K. (2023). How Zambia

132
reduced inequalities in under-five mortality rates over the last two
decades: A mixed-methods study.
BMC Health Services Research, 23(1), 1–15.
https://doi.org/10.1186/s12913-023-
09086-3
Jensen, A. M., Thysen, S. M., Furtado, O., Correia, C., Helleringer, S., von
Bornemann Hjelmborg, J., & Fisker, A. B. (2023). Stillbirth and early
neonatal mortality rates may be underestimated using recall
information: A comparison of demographic surveillance
methodologies. Tropical Medicine & International Health, 28(7),
562–570. https://doi.org/10.1111/tmi.13903
Jorda, V., Niño-Zarazúa, M., & Tejería-Martínez, M. (2024). The lifespan
disparity dataset: An open repository on inequality and polarization in length
of life (1950–
2021). Scientific Data, 11(1). https://doi.org/10.1038/s41597-024-
03426-6
Kaoje, A., Yahaya, M., Raji, M., Hadiza, S., Sylvanus, A., & Musa, T.
(2019). Drinking water quality, sanitation and hygiene practices in a
rural community of Sokoto state, Nigeria. International Journal of
Medical Science and Public Health, 7(11),
Article 1. https://doi.org/10.5455/ijmsph.2019.0824324102018

133
Kayser, G. L., Rao, N., Jose, R., & Raj, A. (2019). Water, sanitation and
hygiene:
Measuring gender equality and empowerment. Bulletin of the World
Health
Organization, 97(6), 438–440. https://doi.org/10.2471/blt.18.223305
Kesmodel, U. S. (2018). Cross-sectional studies - what are they good for?
Acta
Obstetricia et Gynecologica Scandinavica, 97(4), 388–393. Wiley.
https://doi.org/10.1111/aogs.13331
Khan, M. H., Nafees, M., Muhammad, N., Ullah, U., Hussain, R., & Bilal,
M. (2021). Assessment of drinking water sources for water quality,
human health risks, and pollution sources: A case study of the district
Bajaur, Pakistan. Archives of
Environmental Contamination and Toxicology, 80(1), 41–54.
https://doi.org/10.1007/s00244-020-00801-3
Khan, S., & Hancioglu, A. (2019). Multiple Indicator Cluster Surveys:
Delivering robust data on children and women across the globe.
Studies in Family Planning, 50(3),
279–286. https://doi.org/10.1111/sifp.12103
Kilanowski, J. F. (2017). Breadth of the socio-ecological model. Journal of
Agromedicine, 22(4). https://doi.org/10.1080/1059924x.2017.1358971
134
Kipkoech, R., Takase, M., Aliyu, A., Kibet, J., & Mugah, F. (2023).
Availability and accessibility of toilet facilities among low-income
households in selected settlements of Cape Coast Metropolis, Ghana.
Journal of Water, Sanitation and
Hygiene for Development, 13(2).
https://doi.org/10.2166/washdev.2023.197
Kousoulis, A. A., & Goldie, I. (2021). A visualization of a socio-ecological
model for urban public mental health approaches. Frontiers in Public
Health, 9.
https://doi.org/10.3389/fpubh.2021.654011
Lagakos, D. (2020). Urban-rural gaps in the developing world: Does internal
migration offer opportunities? Journal of Economic Perspectives,
34(3), 174–192.
https://doi.org/10.1257/jep.34.3.174
Lakens, D. (2022). Sample size justification. Collabra: Psychology, 8(1).
https://doi.org/10.1525/collabra.33267
Lanfer, H. L., & Reifegerste, D. (2021). Embracing challenging complexity:
Exploring handwashing behavior from a combined socioecological
and intersectional perspective in Sierra Leone. BMC Public Health,
21(1).

135
https://doi.org/10.1186/s12889-021-11923-1
Learn Statistics Easily. (2022, May 19). Sample size in logistic regression: A
simple binary approach. Learn Statistics Easily.
https://statisticseasily.com/2022/05/19/sample-size-logistic-regression/
Leider, J. P., Meit, M., McCullough, J. M., Resnick, B., Dekker, D., Alfonso,
Y. N., & Bishai, D. (2020). The state of rural public health: Enduring
needs in a new decade. American Journal of Public Health, 110(9),
1283–1290. https://doi.org/10.2105/ajph.2020.305728
Lesko, C. R., Ackerman, B., Webster-Clark, M., & Edwards, J. K. (2020).
Target validity: Bringing treatment of external validity in line with
internal validity.
Current Epidemiology Reports, 7(3), 117–124.
https://doi.org/10.1007/s40471-
020-00239-0
Liu, S. (2021). Child mortality and water stress under the framework of
sustainable development goals (SDGs): Evidence from twenty
developing countries. Present
Environment and Sustainable Development, 15(1), 49–58.
https://doi.org/10.15551/pesd2021151004

136
Liwin, L. K., & Houle, B. (2019). The effects of household and community
context on mortality among children under five in Sierra Leone:
Evidence from the 2013
Demographic and Health Survey. Demographic Research, 40, 279–
306.
https://www.jstor.org/stable/26727000
Lu, Z., Bandara, J. S., & Paramati, S. R. (2019). Impact of sanitation, safe
drinking water and health expenditure on infant mortality rate in
developing economies.
Australian Economic Papers, 59(1), 13–33.
https://doi.org/10.1111/1467-
8454.12167
Mahmudiono, T., Segalita, C., & Rosenkranz, R. R. (2019). Socio-ecological
model of correlates of double burden of malnutrition in developing
countries: A narrative review. International Journal of Environmental
Research and Public Health,
16(19), Article 3730. https://doi.org/10.3390/ijerph16193730
Manetu, W. M., & Karanja, A. M. (2021). Waterborne disease risk factors
and intervention practices: A review. OALib, 08(05), 1–11.
https://doi.org/10.4236/oalib.1107401
137
Mebrahtom, S., Worku, A., & Gage, D. J. (2022). The risk of water,
sanitation and hygiene on diarrhea-related infant mortality in eastern
Ethiopia: a populationbased nested case-control. BMC Public Health,
22(1).
https://doi.org/10.1186/s12889-022-12735-7
Mejía-Guevara, I., Zuo, W., Bendavid, E., Li, N., & Tuljapurkar, S. (2019).
Age distribution, trends, and forecasts of under-5 mortality in 31 sub-
Saharan African countries: A modeling study. PLOS Medicine, 16(3),
Article e1002757.
https://doi.org/10.1371/journal.pmed.1002757
Mensch, B. S., Chuang, E. K., Melnikas, A., & Psaki, S. R. (2019). Evidence
for causal links between education and maternal and child health:
Systematic review.
Tropical Medicine & International Health, 24(5).
https://doi.org/10.1111/tmi.13218
Midtgaard Eriksen, C., Lauridsen Kujabi, M., Sulaiman Kanu, A., & Gulis,
G. (2021).
Health perceptions in relation to child health and mortality in a rural
context, Sierra Leone: A mixed method study. International Journal of
Environmental
138
Research and Public Health, 18(1), Article 308.
https://doi.org/10.3390/ijerph18010308
Murtaza, F., Muzaffar, M., Mustafa, T., & Anwer, J. (2021). Water and
sanitation risk exposure in children under-five in Pakistan. Journal of
Family and Community
Medicine, 28(2), Article 103.
https://doi.org/10.4103/jfcm.jfcm_149_21
Naz, L., Patel, K. K., & Uzoma, I. E. (2020). Crucial predicting factors of
under-five mortality in Sierra Leone. Clinical Epidemiology and
Global Health, 8(4), 1121–
1126. https://doi.org/10.1016/j.cegh.2020.04.002
Ngasala, T. M., Masten, S. J., Cohen, C., Ravitz, D., & Mwita, E. (2020).
Implementation of point-of-use water treatment methods in a rural
Tanzanian community: A case study. Journal of Water Sanitation and
Hygiene for Development, 10(4), 1012–
1018. https://doi.org/10.2166/washdev.2020.141
Nunbogu, A. M., Elliott, S. J., & Bisung, E. (2023). I feel the pains of our
past water struggles anytime I turn on the tap: Diaspora perceptions
and experiences of water, sanitation, and hygiene (WaSH) gendered
violence in Ghana. Social
139
Science & Medicine, 317, Article 115621.
https://doi.org/10.1016/j.socscimed.2022.115621
Nwokoro, U. U., Ugwa, O., Chinemerem, O. D., Obi, I. F., Ngozi, M.-O., &
Agunwa, C. (2020). Water, sanitation and hygiene risk factors associated
with diarrhoea morbidity in a rural community of Enugu, South East
Nigeria. Pan African
Medical Journal, 37(1).
https://doi.org/10.11604/pamj.2020.37.115.17735
Obeng, P. A., Obeng, P. A., & Awere, E. (2019). Design and construction of
household ventilated improved pit latrines: Gaps between conventional
technical guidelines and construction practices in Cape Coast, Ghana.
Water Practice and Technology,
14(4), 825–836. https://doi.org/10.2166/wpt.2019.067
Occupational Safety and Health Administration. (n.d.). Sanitation. Osha.gov.
https://www.osha.gov/laws-
regs/regulations/standardnumber/1910/1910.141
Ohwo, O. (2019). Dimensions of inequality in urban and rural water,
sanitation and hygiene services in Sub-Saharan Africa. European
Scientific Journal ESJ, 15(8).
https://doi.org/10.19044/esj.2019.v15n8p144
140
Omarova, A., Tussupova, K., Berndtsson, R., Kalishev, M., & Sharapatova,
K. (2018).
Protozoan Parasites in Drinking Water: A System Approach for
Improved Water,
Sanitation and Hygiene in Developing Countries. International
Journal of
Environmental Research and Public Health, 15(3), Article 495.
https://doi.org/10.3390/ijerph15030495
Osumanu, I. K., Kosoe, E. A., & Ategeeng, F. (2019). Determinants of open
defecation in the Wa municipality of Ghana: Empirical findings
highlighting sociocultural and economic dynamics among households.
Journal of Environmental and Public
Health, 2019, 1–10. https://doi.org/10.1155/2019/3075840
Pouramin, P., Nagabhatla, N., & Miletto, M. (2020). A systematic review of
water and gender interlinkages: Assessing the intersection with health.
Frontiers in Water,
2. https://doi.org/10.3389/frwa.2020.00006
Prasetyo, R. B., Kuswanto, H., Iriawan, N., & Ulama, B. S. S. (2020).
Binomial regression models with a flexible generalized logit link
function. Symmetry, 12(2),
Article 221. https://doi.org/10.3390/sym12020221

141
Prüss-Ustün, A., Wolf, J., Bartram, J., Clasen, T., Cumming, O., Freeman, M.
C., Gordon, B., Hunter, P. R., Medlicott, K., & Johnston, R. (2019).
Burden of disease from inadequate water, sanitation and hygiene for
selected adverse health outcomes: An updated analysis with a focus on
low- and middle-income
countries. International Journal of Hygiene and Environmental
Health, 222(5),
765–777. https://doi.org/10.1016/j.ijheh.2019.05.004
Rakotomanana, H., Komakech, J. J., Walters, C. N., & Stoecker, B. J. (2020).
The WHO and UNICEF Joint Monitoring Programme (JMP)
Indicators for Water Supply, Sanitation and Hygiene and Their
Association with Linear Growth in Children 6 to 23 Months in East
Africa. International Journal of Environmental Research and Public
Health, 17(17), Article 6262. https://doi.org/10.3390/ijerph17176262
Rashid, H. A. (2022, March 28). Research methodology | Importance &
Types of Research Methodology in Research. Library & Information
Management. https://limbd.org/research-methodology-importance-
types-of-researchmethodology-in-research/

142
Ravindra, K., Mor, S., & Pinnaka, V. L. (2019). Water uses, treatment, and
sanitation practices in rural areas of Chandigarh and its relation with
waterborne diseases.
Environmental Science and Pollution Research, 26(19), 19512–19522.
https://doi.org/10.1007/s11356-019-04964-y
Reiner, R. C., Wiens, K. E., Deshpande, A., Baumann, M. M., Lindstedt, P.
A., Blacker,
B. F., Troeger, C. E., Earl, L., Munro, S. B., Abate, D., Abbastabar, H.,
AbdAllah, F., Abdelalim, A., Abdollahpour, I., Abdulkader, R. S.,
Abebe, G., Abegaz, K. H., Abreu, L. G., Abrigo , M. R. M., & Hay, S.
I. (2020). Mapping geographical inequalities in childhood diarrhoeal
morbidity and mortality in lowincome and middle-income countries,
2000–17: Analysis for the global burden of disease study 2017. The
Lancet, 395(10239), 1779–1801. https://doi.org/10.1016/S0140-
6736(20)30114-8
Rheingans, R., Anderson, J. D., Luyendijk, R., & Cumming, O. (2013).
Measuring disparities in sanitation access: does the measure matter?
Tropical Medicine &
International Health, 19(1), 2–13. https://doi.org/10.1111/tmi.12220

143
Rudolph, J. E., Zhong, Y., Duggal, P., Mehta, S. H., & Lau, B. (2023).
Defining representativeness of study samples in medical and
population health research.
BMJ Medicine, 2(1), Article e000399. https://doi.org/10.1136/bmjmed-
2022-
000399
Russell, F., & Azzopardi, P. (2019). WASH: a basic human right and essential
intervention for child health and development. The Lancet Global
Health, 7(4),
Article e417. https://doi.org/10.1016/s2214-109x(19)30078-6
Salihu, H., Wilson, R. E., King, L. M., Marty, P. J., & Whiteman, V. E.
(2015). Socioecological Model as a Framework for Overcoming
Barriers and Challenges in
Randomized Control Trials in Minority and Underserved
Communities.
International Journal of MCH and AIDS (IJMA), 3(1).
https://doi.org/10.21106/ijma.42
Salzberg, N. T., Sivalogan, K., Bassat, Q., Taylor, A. W., Adedini, S., El
Arifeen, S.,
Assefa, N., Blau, D. M., Chawana, R., Cain, C. J., Cain, K. P., Caneer,
J. P.,

144
Garel, M., Gurley, E. S., Kaiser, R., Kotloff, K. L., Mandomando, I.,
Morris, T.,
Nyamthimba Onyango, P., & Child Health and Mortality Prevention
Surveillance (CHAMPS) Methods Consortium. (2019). Mortality
surveillance methods to identify and characterize deaths in child health
and mortality prevention surveillance network sites. Clinical
Infectious Diseases, 69(Supplement_4),
S262–S273. https://doi.org/10.1093/cid/ciz599
Scarneo, S. E., Kerr, Z. Y., Kroshus, E., Register-Mihalik, J. K., Hosokawa,
Y., Stearns, R. L., DiStefano, L. J., & Casa, D. J. (2019). The
socioecological framework: A multifaceted approach to preventing
sport-related deaths in high school sports.
Journal of Athletic Training, 54(4), 356–360.
https://doi.org/10.4085/1062-6050-
173-18
Sesay, B. P., Hakizimana, J. L., Elduma, A. H., & Gebru, G. N. (2022).
Assessment of
Water, Sanitation and Hygiene Practices Among Households, 2019 −
Sierra Leone: A Community-based Cluster Survey. Environmental
Health Insights, 16.

145
https://doi.org/10.1177/11786302221125042
Setia, M. S. (2016). Methodology series module 3: Cross-sectional studies.
Indian
Journal of Dermatology, 61(3), 261–264. NCBI.
https://doi.org/10.4103/0019-
5154.182410
Sharma Waddington, H., & Cairncross, S. (2021). PROTOCOL: Water,
sanitation and hygiene for reducing childhood mortality in low‐ and
middle‐income countries.
Campbell Systematic Reviews, 17(1). https://doi.org/10.1002/cl2.1135
Sidani, S., & O’Rourke, H. (2020). Quantitative and qualitative strategies to
strengthen internal validity in randomized trials. Canadian Journal of
Nursing Research,
54(1), Article 084456212097419.
https://doi.org/10.1177/0844562120974197
Sierra Leone life expectancy 1950-2019. (n.d.). Macrotrends.net.
https://www.macrotrends.net/countries/SLE/sierra-leone/life-
expectancy
Sierra Leone literacy rate 2004-2023. (n.d.). Www.macrotrends.net.
https://www.macrotrends.net/countries/SLE/sierra-
leone/literacyrate#:~:text=Adult%20literacy%20rate%20is%20the
146
Smiti, A. (2020). A critical overview of outlier detection methods. Computer
Science
Review, 38, Article 100306.
https://doi.org/10.1016/j.cosrev.2020.100306
Sridhar, M. K. C., Okareh, O. T., & Mustapha, M. (2020). Assessment of
knowledge, attitudes, and practices on water, sanitation, and hygiene
in some selected LGAs in Kaduna state, northwestern Nigeria. Journal
of Environmental and Public
Health, 2020, 1–14. https://doi.org/10.1155/2020/6532512
Ssemugabo, C., Halage, A. A., Namata, C., Musoke, D., & Ssempebwa, J. C.
(2020). A socio-ecological perspective of the facilitators and barriers
to uptake of water, sanitation and hygiene interventions in a slum
setting in Kampala, Uganda: a qualitative study. Journal of Water,
Sanitation and Hygiene for Development, 10(2), 227–237.
https://doi.org/10.2166/washdev.2020.124
Statistics Sierra Leone. (2018). Sierra Leone Multiple Indicator Cluster
Survey 2017,
Survey Findings Report. Freetown, Sierra Leone: Statistics Sierra
Leone.
https://mics.unicef.org/sites/mics/files/Sierra%20Leone%202017%20
MICS%20S urvey%20Findings%20Report_English.pdf
147
Statistics Solutions. (n.d.). Assumptions of logistic regression. Statistics
Solutions.
https://www.statisticssolutions.com/free-resources/directory-of-
statisticalanalyses/assumptions-of-logistic-regression/
Sultana, R., Nahar, N., Luby, S. P., Swarna, S. T., Gurley, E. S., Tamason, C.
C., Khan,
S. I., Rimi, N. A., Kabir, H., Saifullah, Md. K., Howlader, S. R., &
Kjær, P. (2022). Measuring water quantity used for personal and
domestic hygiene and determinants of water use in a low-income
urban community. International Journal of Environmental Research
and Public Health, 19(23), Article 15656.–
https://doi.org/10.3390/ijerph192315656
Swe, K. T., Rahman, Md. M., Rahman, Md. S., Teng, Y., Abe, S. K.,
Hashizume, M., & Shibuya, K. (2021). Impact of poverty reduction on
access to water and sanitation in low‐ and lower‐middle‐income
countries: Country‐specific Bayesian projections to 2030. Tropical
Medicine & International Health, 26(7), 760–774.
https://doi.org/10.1111/tmi.13580
Tagoe, E. T., Agbadi, P., Nakua, E. K., Duodu, P. A., Nutor, J. J., & Aheto, J.
M. K. (2020). A predictive model and socioeconomic and

148
demographic determinants of under-five mortality in Sierra Leone.
Heliyon, 6(3), Article e03508.
https://doi.org/10.1016/j.heliyon.2020.e03508
Tesema, G. A., Teshale, A. B., & Tessema, Z. T. (2021). Incidence and
predictors of under-five mortality in East Africa using multilevel
Weibull regression modeling.
Archives of Public Health, 79(1). https://doi.org/10.1186/s13690-021-
00727-9
Tessema, R. A., & Alemu, B. M. (2021). Adequacy of improved sources of
drinking water, sanitation, and hygiene practice for the reduction of
diarrheal disease among people living with HIV/AIDS, Harar region,
Ethiopia. HIV/AIDS
(Auckland, N.Z.), 13, 1–11. https://doi.org/10.2147/HIV.S286976
Thomson, K., Hillier-Brown, F., Todd, A., McNamara, C., Huijts, T., &
Bambra, C. (2018). The effects of public health policies on health
inequalities in high-income countries: An umbrella review. BMC Public
Health, 18(1).
https://doi.org/10.1186/s12889-018-5677-1
Tripathy, J. P. (2013). Secondary data analysis: Ethical issues and challenges.
Iranian
149
Journal of Public Health, 42(12), 1478–1479. NCBI.
https://www.ncbi.nlm.nih.gov/pmc/articles/PMC4441947/
Tseole, N. P., Mindu, T., Kalinda, C., & Chimbari, M. J. (2022). Barriers and
facilitators to Water, Sanitation and Hygiene (WaSH) practices in
Southern Africa: A scoping review. PLOS ONE, 17(8), Article
e0271726.
https://doi.org/10.1371/journal.pone.0271726
Tumwebaze, I. K., Hrdličková, Z., Labor, A., Turay, A., Macarthy, J. M.,
Chmutina, K., Scott, R., Kayaga, S., Koroma, B., & Howard, G.
(2022). Water and sanitation service levels in urban informal
settlements: A case study of Portee-Rokupa in
Freetown, Sierra Leone. Journal of Water, Sanitation and Hygiene for
Development, 12(8). https://doi.org/10.2166/washdev.2022.115
Turienzo, C. F., November, L., Kamara, M., Kamara, P., Goodhart, V.,
Ridout, A., Sam, B., Thomas, S., Williams, P. T., Sandall, J., &
Shennan, A. H. (2022). Innovations to reduce maternal mortality and
improve health and wellbeing of adolescent girls and their babies in
Sierra Leone. The Lancet Child & Adolescent Health, 0(0).
https://doi.org/10.1016/S2352-4642(22)00322-4

150
Ugboko, H. U., Nwinyi, O. C., Oranusi, S. U., & Oyewale, J. O. (2020).
Childhood diarrhoeal diseases in developing countries. Heliyon, 6(4),
Article e03690. https://doi.org/10.1016/j.heliyon.2020.e03690
United Nations Children's Fund. (n.d.-a). About MICS. Mics.unicef.org.
https://mics.unicef.org/about
United Nations Children's Fund. (n.d.-b). Water, sanitation and hygiene: Low
access to
WASH services is affecting the health, survival and development of
children in
Sierra Leone. https://www.unicef.org/sierraleone/water-sanitation-and-
hygiene
United Nations Children's Fund. (n.d.-c). Water, sanitation and hygiene: Safe
water, toilets and good hygiene keep children alive and healthy.
https://www.unicef.org/wash
United Nations Children's Fund. (2018, July 6). UNICEF MICS. Unicef.org.
https://mics.unicef.org/methodological_work/3/WATER-QUALITY
United Nations Children's Fund. (2023, January). Under-five mortality.
UNICEF DATA. https://data.unicef.org/topic/child-survival/under-
five-mortality/
University of Minnesota School of Public Health. (2015, February 20). About
the socioecological model .

151
https://mch.umn.edu/sem/#:%7E:text=The%20%E2%80%9Csocio%2
Decological
%20model%E2%80%9D
van Cooten, M. H., Bilal, S. M., Gebremedhin, S., & Spigt, M. (2018). The
association between acute malnutrition and water, sanitation, and
hygiene among children aged 6–59 months in rural Ethiopia. Maternal
& Child Nutrition, 15(1).
https://doi.org/10.1111/mcn.12631
Van Malderen, C., Amouzou, A., Barros, A. J. D., Masquelier, B., Van Oyen,
H., & Speybroeck, N. (2019). Socioeconomic factors contributing to under-
five mortality in sub-Saharan Africa: A decomposition analysis. BMC Public
Health,
19(1). https://doi.org/10.1186/s12889-019-7111-8
Vatcheva, K. P., & Lee, M. (2016). Multicollinearity in regression analyses
conducted in epidemiologic studies. Epidemiology: Open Access,
06(02).
https://doi.org/10.4172/2161-1165.1000227
Waddington, H. S., Masset, E., Bick, S., & Cairncross, S. (2023). Impact on
childhood mortality of interventions to improve drinking water,
sanitation, and hygiene

152
(WASH) to households: Systematic review and meta-analysis. PLOS
Medicine,
20(4), Article e1004215.
https://doi.org/10.1371/journal.pmed.1004215
Walden University. (n.d.). SPSS and NVIVO. Academicguides.waldenu.edu.
https://academicguides.waldenu.edu/academic-skills-center/course-
levelstatistics/spss-nvivo#s-lg-box-wrapper-31414632
Winking, J. (2016). Child mortality. Encyclopedia of Evolutionary
Psychological
Science, 1–7. https://doi.org/10.1007/978-3-319-16999-6_102-1
Wolf, J., Hunter, P. R., Freeman, M. C., Cumming, O., Clasen, T., Bartram,
J., Higgins, J. P. T., Johnston, R., Medlicott, K., Boisson, S., & Prüss-
Ustün, A. (2018). Impact of drinking water, sanitation and
handwashing with soap on childhood diarrhoeal disease: Updated
meta-analysis and meta-regression. Tropical
Medicine & International Health, 23(5), 508–525.
https://doi.org/10.1111/tmi.13051
The World Bank. (n.d.). UNICEF Multiple Indicator Cluster Surveys (MICS).
Microdata.worldbank.org.
https://microdata.worldbank.org/index.php/collections/MICS
World Food Programme. (n.d.). Sierra Leone. Wfp.org.

153
https://www.wfp.org/countries/sierra-leone
World Health Organization. (n.d.). Multiple indicator cluster survey 6
(MICS6). SCORE for Health Data.
https://score.tools.who.int/tools/survey-populations-and-
healthrisks/tool/multiple-indicator-cluster-survey-6-mics6-3/
World Health Organization. (2022, January 28). Child mortality (under 5
years). Www.who.int. https://www.who.int/news-room/fact-
sheets/detail/levels-andtrends-in-child-under-5-mortality-in-2020
World Health Organization. (2023, December 21). Sierra Leone launches
national public health agency to strengthen healthcare infrastructure.
WHO | Regional Office for Africa.
https://www.afro.who.int/countries/sierra-leone/news/sierra-
leonelaunches-national-public-health-agency-strengthen-healthcare-
infrastructure
Worldometer. (2023, July 16). Sierra Leone population . Worldometers.info.
https://www.worldometers.info/world-population/sierra-leone-
population/
Yaya, S., Uthman, O. A., Okonofua, F., & Bishwajit, G. (2019).
Decomposing the ruralurban gap in the factors of under-five mortality

154
in sub-Saharan Africa? Evidence from 35 countries. BMC Public
Health, 19(1). https://doi.org/10.1186/s12889-
019-6940-9
Young, S. L., Bethancourt, H. J., Ritter, Z. R., & Frongillo, E. A. (2022).
Estimating national, demographic, and socioeconomic disparities in
water insecurity experiences in low-income and middle-income
countries in 2020–21: A crosssectional, observational study using
nationally representative survey data. The
Lancet Planetary Health, 6(11), e880–e891.
https://doi.org/10.1016/s2542-
5196(22)00241-8
Zerbo, A., Castro Delgado, R., & Arcos González, P. (2021). Water sanitation
and hygiene in sub-Saharan Africa: Coverage, risks of diarrheal
diseases, and urbanization. Journal of Biosafety and Biosecurity, 3(1),
41–45.
https://doi.org/10.1016/j.jobb.2021.03.004
Zewudie, A. T., Gelagay, A. A., & Enyew, E. F. (2020). Determinants of
under-five child mortality in Ethiopia: Analysis using Ethiopian
Demographic Health Survey,
2016. International Journal of Pediatrics, 2020, 1–9.

155
https://doi.org/10.1155/2020/7471545
Gaffan, N., Kpozehouen, A., Dégbey, C., Ahanhanzo, Y. G., & Paraïso, M. N.
(2023). Effects of household access to water, sanitation, and hygiene
services on underfive mortality in Sub-Saharan Africa. 11.
https://doi.org/10.3389/fpubh.2023.1136299
Headey, D., & Palloni, G. (2019). Water, sanitation, and child health:
Evidence from subnational panel data in 59 countries. Demography,
56(2), 729–752. https://doi.org/10.1007/s13524-019-00760-y
Russell, F., & Azzopardi, P. (2019). WASH: a basic human right and essential
intervention for child health and development. The Lancet Global Health,
7(4),
Article e417. https://doi.org/10.1016/s2214-109x(19)30078-6
Sharma Waddington, H., & Cairncross, S. (2021). PROTOCOL: Water,
sanitation and hygiene for reducing childhood mortality in low‐ and
middle‐income countries.
Campbell Systematic Reviews, 17(1). https://doi.org/10.1002/cl2.1135
Thomson, K., Hillier-Brown, F., Todd, A., McNamara, C., Huijts, T., &
Bambra, C. (2018). The effects of public health policies on health
inequalities in high-income countries: An umbrella review. BMC
Public Health, 18(1).

156
https://doi.org/10.1186/s12889-018-5677-1
Waddington, H. S., Masset, E., Bick, S., & Cairncross, S. (2023). Impact on
childhood mortality of interventions to improve drinking water,
sanitation, and hygiene
(WASH) to households: Systematic review and meta-analysis. PLOS
Medicine,
20(4), Article e1004215.
https://doi.org/10.1371/journal.pmed.1004215
Zewudie, A. T., Gelagay, A. A., & Enyew, E. F. (2020). Determinants of
under-five child mortality in Ethiopia: Analysis using Ethiopian
Demographic Health Survey,
2016. International Journal of Pediatrics, 2020, 1–9.
https://doi.org/10.1155/2020/7471545

