


1
What Can and Cannot be Said: Discourses of Spirituality and Religion in
Clinical Psychology
Introduction
The United Kingdom (UK) is a nation of increasing religious diversity.
Minority religions are steadily growing, particularly Islam, while a significant but
declining percentage of individuals identify as Christian (Office for National
Statistics, 2012). Whilst the census may over-represent religious affiliation
(Zurlo & Johnson, 2016; YouGov, 2014), many people endorse some
nontheistic spiritual beliefs (Ipsos MORI, 2007). Spirituality and religion are
personally meaningful for many individuals with mental health difficulties (Hefti,
2011), including depression (Fitchett, Burton, & Sivan, 1997; Bosworth, Park,
McQuoid, Hays, & Steffens, 2003), schizophrenia (Mohr, Brandt, Borras,
Gilliéron, & Huguelet, 2006), substance misuse (Flynn, Joe, Broome, Simpson,
& Brown, 2003) and physical comorbidities (Hebert, Zdaniuk, Schulz, & Scheier,
2009).
National documents recommend attending to the religious and spiritual
preferences and needs of service users across a range of settings where
clinical psychologists (CPs) work (Commission for Healthcare Audit and
Inspection, 2007; Department of Health, 2009; Mental Health Foundation, 2006;
Royal College of Psychiatrists, 2013). However, there is no guidance specific to

SPIRITUALITY IN CLINICAL PSYCHOLOGY 2
UK psychology, other than that it should be addressed as an area of diversity
(British Psychological Society [BPS], 2009; Health Professions Council, 2008)
and considered in a culturally sensitive formulation (BPS, 2011).
Practitioners can be hesitant to bring up spirituality if not first introduced by
the client (Lee & Baumann, 2013), but many clients who value religion do not
raise it with their clinicians (Huguelet, Mohr, Borras, Gillieron, & Brandt, 2006).
Individuals in the UK who hold spiritual beliefs report using them to cope with
psychological problems (Mayers, Leavey, Vallianatou, & Barker, 2007), and
voice concerns that secular-based help may be insensitive to their beliefs, or
weaken their faith (Mayers et al., 2007; Mitchell & Baker, 2000). Clinicians are
often unaware that clients experience conflict between their spiritual beliefs and
treatment (Huguelet et al., 2006).
Spirituality may be an unfamiliar concept for many CPs. Research in the
United States of America (US) has found that psychologists report lower levels
of religious affiliation and spirituality than the general population, or other mental
health professions (Bergin & Jensen, 1990; Bilgrave & Deluty, 1998).
Worryingly, a mismatch between clinician and client ideology has been linked to
reduced therapist empathy, and assessments of clients as less mature and less
open to therapy (Gartner, Harmatz, Hohmann, Larson, & Gartner, 1990).
Research suggests that many professionals pathologise religious beliefs and
practices (McClure & Livingston, 2000), whilst even those who view spirituality
as important rarely discuss it (Ellis, Vinson, & Ewigman, 1999).
If spirituality is of high importance to clients, but not addressed in
therapeutic work individuals may drop out of therapy, potentially influencing both
current and future treatment outcomes. The attitudes of CPs to spirituality may

SPIRITUALITY IN CLINICAL PSYCHOLOGY 3
further impact treatment efficacy via the therapeutic alliance, which may be
more difficult to establish if CPs take a negative view of those with religious
beliefs (Gartner et al, 1990 and McClure & Livingston, 2000) or clients percieve
beliefs which are important to them as being overlooked. Without an
understanding of CP attitudes to spirituality and religion in the UK this cannot be
assessed or addressed.
There is evidence that spiritual beliefs and/or practices benefit physical
and emotional wellbeing for some individuals (Larson & Larson, 2003), including
those with mental health diagnoses (Mohr et al., 2006). However, religion has
been used to legitimise both physical and emotional abuse (Capps, 1992), and
religious distress can exacerbate negative emotional states (Exline, Yali, &
Lobel, 1999). Negative experiences with spirituality or religion can have a
detrimental impact on mental health, increasing a person’s sense of alienation,
depression and hopelessness (Bussema & Bussema, 2000; Exline, 2002;
Exline, Yali, & Sanderson, 2000).
Whether the impact is positive or negative, an individual’s spiritual history,
practice and beliefs, should be assessed if the most comprehensive support
and accurate formulation is to be developed (Hathaway, Scott, & Garver, 2004).
Spiritual beliefs and practices can influence individuals’ worldviews, social
functioning and expressions of distress (Mitchell & Baker, 2000; Richards &
Bergin, 1997).
Defining Religion and Spirituality
The terms spirituality and religion are difficult to separate and some have
recommended that they remain undifferentiated in research (Oman, 2013;

SPIRITUALITY IN CLINICAL PSYCHOLOGY 4
Masters, 2010). However, they are distinct constructs (Saucier & Skrzypińska,
2006), with some groups being more likely to describe themselves as spiritual
than religious (Phillips, 2010). Spirituality is considered an umbrella term
concerned with individual experiences and personal meaning (Zinnbauer &
Pargament, 2005), with religion forming a subset of spirituality as expressed in
behaviour and rituals (Huguelet & Koenig, 2009). The term spirituality is used
here to encompass both broader spirituality and religion.
Systematic Review Rationale
Despite increasing interest in spirituality within UK clinical psychology,
there have been no systematic reviews of the literature to determine how CPs in
the UK address this area. Much of the literature on spirituality in clinical
psychology practice originates in the US. There are significant cultural and
demographic differences between the UK and the US, with religion forming a
larger part of mainstream culture in America. Only 15% of the US population
report having no religious affiliation (United States Census Bureau, 2010),
compared to 25% in England and Wales (Office for National Statistics, 2011).
Unlike the UK, some accredited training courses in the US are run by explicitly
religious institutions (Campbell, 2011). The substantial variations in healthcare
delivery between the two countries also mean that evidence from America must
be treated with caution when extrapolating to the UK.
Clinicians’ attitudes towards spiritual issues appear to influence whether
service users raise them in appointments (Koenig, Bearon, & Dayringer, 1989).
Personal attitudes have also been found to influence therapeutic practice more
than clinical training (Shafranske & Malony, 1990). It is therefore important to

SPIRITUALITY IN CLINICAL PSYCHOLOGY 5
review the current literature to gain an understanding of UK CPs’ attitudes
towards spirituality in their professional practice.
Aim of the Review
This systematic review aimed answer the question: What are the attitudes,
beliefs and practices of CPs in the UK regarding raising, considering or
discussing spiritual issues in any part of their practice? Critically evaluating and
compiling these findings was considered helpful as research in this area
remains sparse, with the majority carried out in the US.
Methods
This systematic review was conducted using an adapted version of the
Preferred Reporting Items for Systematic Reviews and Meta-Analyses
(PRISMA) reporting protocol (Moher, Liberati, Tetzlaff, & Altman, 2009). It is
important to follow clear guidelines to ensure that a review is systematic,
unbiased and repeatable. The PRISMA guidelines were developed with a focus
on randomised trials, and are particularly designed for evaluations of
interventions (PRISMA Homepage, 2015). Adaptation was therefore necessary,
as some aspects were less relevant for qualitative, non-interventive studies. For
example, the focus on PICOS (participants, interventions, comparators,
outcomes, study design) required alteration, with participants’ occupation and
location, and the concepts studied, instead forming the inclusion and exclusion
criteria.
As there has not been extensive research into this area in the UK, the
search terms were kept broad to ensure all relevant papers would be captured.
The searches comprised the following terms:

SPIRITUALITY IN CLINICAL PSYCHOLOGY 6
1 spiritual*
2 religio*
3 faith
4 sacred
5 clinical psycholog*
6 1 OR 2 OR 3 OR 4
7 6 AND 5
The search terms were applied to the PubMed, PsychInfo and Web of
Knowledge databases in line with their respective search grammars and
structures (Appendix A).
Screening Procedure
Inclusion/Exclusion Criteria. Inclusion criteria were studies where the
participants were CPs working and/or training in the UK. Studies which
examined more than one profession were included if clinical psychology results
were reported separately, or formed the majority (>50%) of the sample with
other professions being closely allied to clinical psychology (i.e., counselling
psychologists, psychological therapists, counsellors, psychoanalysts). Both
quantitative and qualitative papers were included if they constituted research
into the beliefs, attitudes, or practices of clinical psychology as related to
spirituality. This included surveys of professional practice, questionnaire
assessment of beliefs or practice which specifically ask about spiritual or
religious matters, and qualitative research addressing spirituality and/or religion.
Initial screening of titles and abstracts was carried out to identify
potentially relevant papers. Research papers where the participants were not
CPs, for example those looking at nursing attitudes or service user experience,

SPIRITUALITY IN CLINICAL PSYCHOLOGY 7
were excluded. Where participants were clearly identified as practising outside
the UK papers were also excluded at this stage.
The remaining papers were accessed in full where possible and screened
to check that they were original research, carried out with CPs from the UK, and
addressing spirituality in relation to clinical practice (including training).
Duplicate results or papers based on duplicate data were excluded at this
stage. The grey literature was searched via GoogleScholar and the British
Library’s electronic record of UK doctoral theses (EThOS), using the terms
above. A manual search of the references of identified papers was also carried
out. Finally, the resulting cohort of studies was quality assessed, using the
critical appraisal skills programme (CASP) qualitative checklist (CASP, 2013) to
evaluate qualitative studies in the sample. One point was awarded for each
criterion fully met (Appendix B).
Results
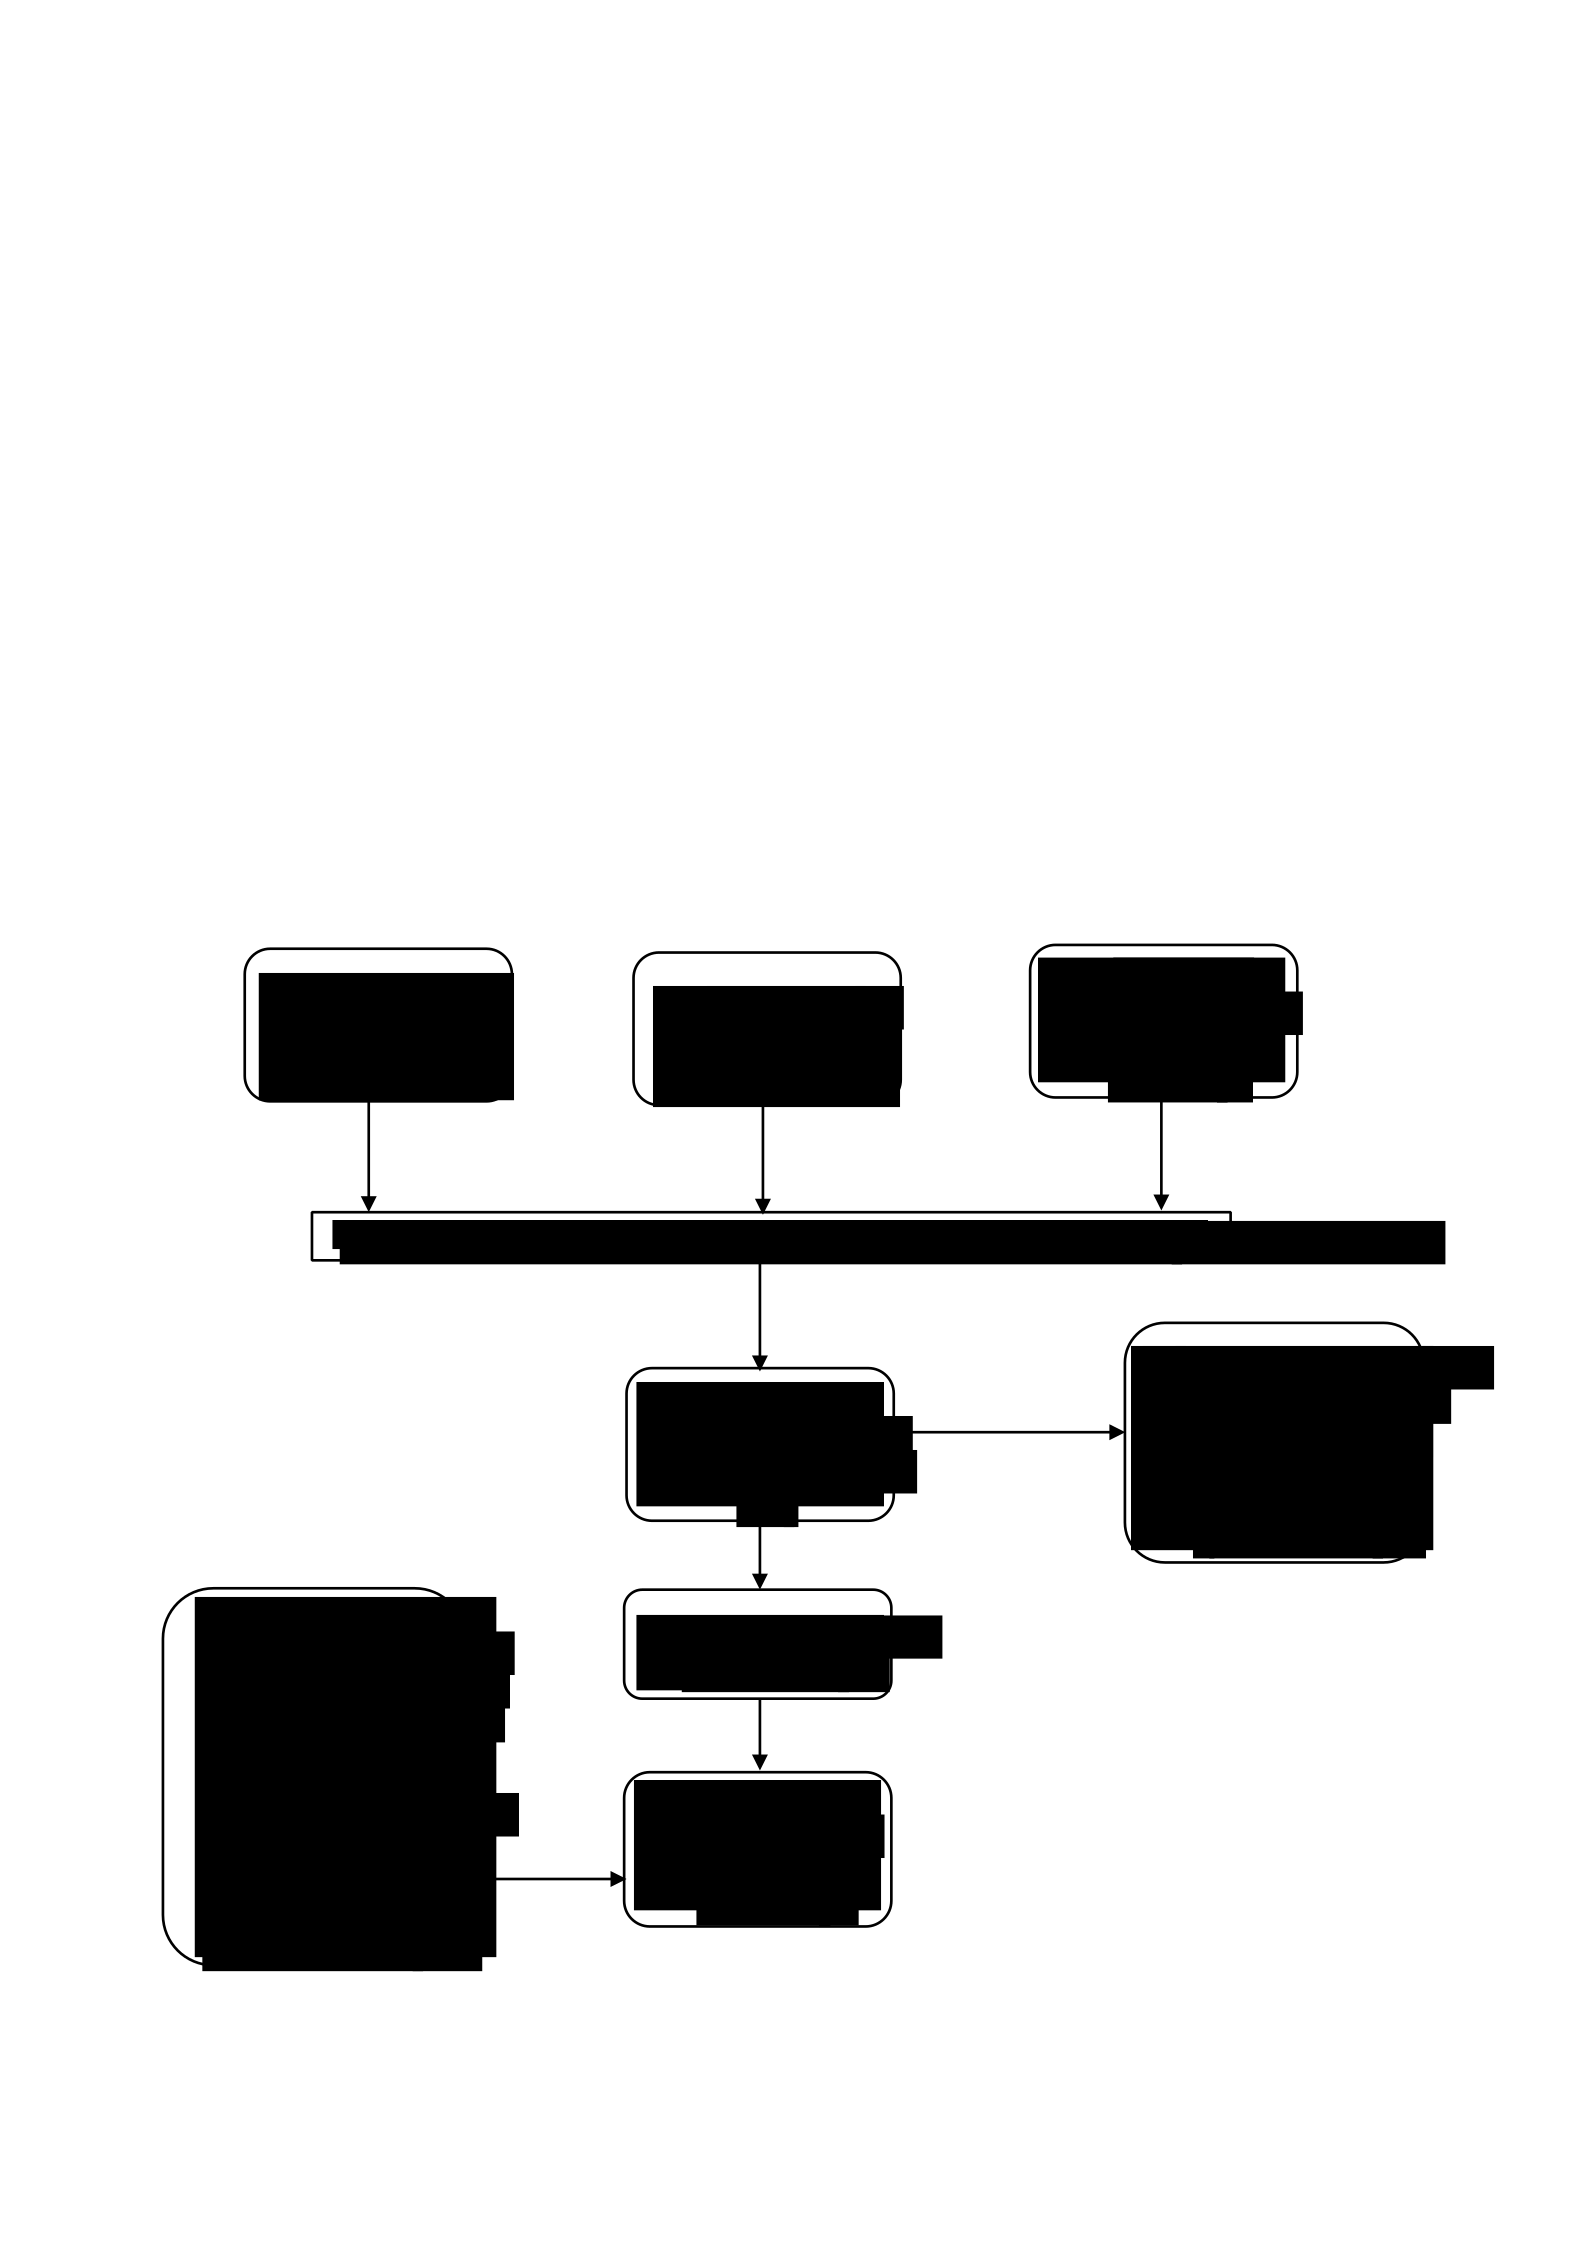
The initial searches of the PubMed, PsychInfo and Web of Knowledge
databases returned 2,804, 3,728 and 94 results respectively, totalling 6,626
records (including duplications). After applying inclusion and exclusion criteria to
titles and abstracts, 28 articles remained. Most papers were excluded from titles
only, as they focussed on non-psychology professionals, client outcomes or
client population characteristics. After reviewing abstracts, papers which
included CPs but were carried out outside the UK (mainly in the US), or did not
report original research, were excluded.
Of the 28 papers reviewed in full, 25 were excluded due to not meeting
inclusion criteria. Fifteen studies were conducted exclusively outside the UK,
with a further three not including UK psychologists in their sample. Three
SPIRITUALITY IN CLINICAL PSYCHOLOGY 8
papers did not state where participants lived and worked. However, as all
authors worked at US institutions or the articles were published in US state
journals, they were excluded. Two papers did not report original research and
two were based on duplicated data. Three papers remained for inclusion in the
qualitative synthesis.
A search of the grey literature (GoogleScholar and EThOS) was
undertaken using the search terms above. Six additional results meeting
inclusion criteria were identified from these sources. Finally, a manual search of
the references of identified papers returned a further four studies that met
inclusion criteria, giving a total of thirteen papers for review.
Figure 1. Flow diagram showing the number of records identified and excluded
through the different phases of the review.
PubMed
2804
results
returned
PsychInfo
results
3728
returned
Web of
Knowledge
94
results
returned
Titles and abstracts screened for inclusion and exclusion criteria
papers
28
remaining for
scree
ning of full
text
25
papers excluded
:
non
18
-
UK sample
2
not research
not clinical
3
psychology
2
duplications
Search of grey
literature (Google
Scholar & EthOS)
:
6
results meeting
inclusion criteria
Searching papers
referenced by
i
nclu
ded results
:
results
4
meeting
inclusion criteria
1
3
papers
included in
qualitative
synthesis
papers eligible
3
for inclusion

9
Running head: SPIRITUALITY IN CLINICAL PSYCHOLOGY
Table 1
Summary of main findings from the systematic review
Reference
CASP
Score
Aim
Design and
Analysis
Data
Risk of bias/
Limitations
Findings and Clinical Relevance
Arshad, R. (2007).
How do clinical
psychologists work
with religious themes
in psychosis?
(Doctoral dissertation).
Retrieved from British
Library e-thesis online
service
(uk.bl.ethos.697398)
7/8
How do clinical
psychologists
address religious
themes in work
with individuals
with psychosis.
Including how
their values may
impact their
practice in this
area.
Qualitative
study.
Grounded
Theory
analysis of
interview
transcripts.
Semi
structured
interviews
with 10
qualified
clinical
psychologists
working with
psychosis for
over a year.
Volunteers likely
to have a
particular
interest in this
area.
Response rate
is not clear.
Notes that the
identity of the
researcher as a
British Muslim
would influence
both the
interviews and
analysis.
Core category ‘unravelling’ and three
main categories; defining roles,
unpicking cases and interacting with
religious themes.
Highlighted limited guidance, lack of
reflection and the defined boundaries
of the clinical psychologist role (we
don’t impose our beliefs and work to
reduce distress).
Challenging; drawing out discrepancies
between the individual’s beliefs and a
religious source to which the client
attributes authority and meaning. The
area is seen as “hard work” in part due
to the “impermeability of a higher
power” to challenge.

SPIRITUALITY IN CLINICAL PSYCHOLOGY 10
Baker, M. & Wang, M.
(2004). Examining
connections between
values and practice in
religiously committed
U.K. clinical
psychologists. Journal
of Psychology and
Theology, 32(2),
126136.
6/8
To investigate the
interaction of
personal
Christian values,
and clinical
psychological
practice.
Qualitative
study.
Grounded
theory
analysis of
semistructured
phone
interview
transcripts,
based on
repertory grid
responses.
Telephone
interviews
with 14
qualified
clinical
psychologists
who were
working in the
NHS and
members of
“network of
Christians in
psychology”.
Lack of
consideration
of the influence
of the
researcher on
the interviews
and analysis.
Acknowledges
that the
sample is likely
to hold extreme
rather than
representative
views.
Added value: enhanced performance
and spiritual support.
Speaking Out: religious disclosure to
colleagues, and to clients. This was an
area of tension, as training advocated
non-disclosure. Hostility and disrespect
were expected from colleagues.
Challenge: value clash between beliefs
and wider society or psychology.
Harmony: value congruence with
nonjudgement and respect.
The Big Picture: the sense of broader
involvement in kingdom of God and as
psychologists who were also members
of the Christian community.

SPIRITUALITY IN CLINICAL PSYCHOLOGY 11
Begum, N. (2012).
Trainee clinical
psychologists talking
about religion and
spirituality in their work
(Doctoral dissertation).
Retrieved from British
Library e-thesis online
service (uk.bl.ethos.
575830)
6/8
To explore
trainee clinical
psychologists’
experiences of
religion and
spirituality, and
how this relates
to and impacts
upon their
professional
training.
Including how
trainee clinical
psychologists
define and
understand their
own values with
regards to
religion and
spirituality.
Qualitative
study.
Interpretive
phenomenolo
gical analysis
(IPA) on
transcripts of
semistructured
interviews.
Eight
interviews
with 2nd and
3rd year
clinical
psychology
trainees.
Opportunistic
sampling via
word of mouth.
The sample
were all white
female trainees.
Use of IPA at
odds with the
fact that
individuals
talked
academically
rather than
about their
experience.
Conceptualising religion and
spirituality: spirituality as free-flowing,
yet ‘containing’ religion which is rigid. A
preference for spirituality was stated,
but the majority of discussion covered
religion, which seemed easier to
consider.
Self within a religious/ spiritual context:
Influences (e.g. family and school) and
identity (e.g. spiritual but not religious
or Jewish but not believing in God)
Experiences of religion and spirituality
as a trainee clinical psychologist:
shared framework with clients (or lack
of). Belief is not actively explored.
Topics are hard to bring to supervision
if not shared with supervisor or client.
Culture and stereotypes, assuming
more relevance for ethnic minorities.
‘There’s no space for religion’;
attributing blame. Clinical psychology
as tending not to address religion and
spirituality although it could. The
profession as mirroring secular society
and scientist-practitioner model being
inconsistent with religion or spirituality.
Facilitating religion and spirituality –
finding less stigmatising words to use
(e.g. faith, strengths or values rather
than spirituality/religion) and struggling
to articulate themselves, as these
topics are difficult to think and talk
about.

SPIRITUALITY IN CLINICAL PSYCHOLOGY 12

SPIRITUALITY IN CLINICAL PSYCHOLOGY 13
Betteridge, S. (2012).
Exploring the clinical
experiences of Muslim
psychologists in the
UK when working with
religion in therapy
(Doctoral dissertation).
Retrieved from British
Library e-thesis online
service
(uk.bl.ethos.637577)
6/8
How do Muslim
psychologists
trained in the UK
experience
religion in a
therapeutic
setting and
what does it
mean to them?
How do the
religious beliefs
of Muslim
psychologists in
the UK impact
upon their
therapeutic
approach with
religious clients?
Qualitative
study.
Grounded
theory
analysis of
semistructured
interview
transcripts.
Interviews
with six
qualified
psychologists
who identified
as Muslim.
Four clinical
psychologists,
two
counselling
psychologists.
Sampling bias
due to
emailing
people whose
names
appeared to be
Muslim. Lack
of clarity in
write up
between
cultural and
religious
Muslim
identities of
participants.
Religious journeys in therapy:
Important to listen, give permission to
discuss religion, respect potential
importance and be at ease with
religious language.
Therapeutic approaches: Adapt
models to fit with the client and their
religious beliefs; use explicitly religious
strategies; identify and encourage
religious strategies used previously.
Therapeutic relationship: Matching
religion may not be beneficial.
Therapists enjoy work with shared
beliefs more. When relevant, difference
should be proactively addressed.
Therapist’ identity: Personal beliefs
impact management of religion in
therapy. Disclosure was seen as
complicated by religious dress and
most helpful to other Muslims. Context
of therapy: NHS limits time, modality,
and discussion of religion.
Cultural context of ‘islamophobia’.

SPIRITUALITY IN CLINICAL PSYCHOLOGY 14
Crossley, J. P. & Salter,
D. P. (2005). A question
of finding harmony: A
grounded
theory study of clinical
psychologists’
experience of
addressing spiritual
beliefs in therapy.
Psychology and
Psychotherapy:
Theory, Research and
Practice, 78, 295–313.
5/8
To develop an
account of the
way in which
clinical
psychologists
understand and
address
spirituality within
therapy.
Qualitative
study.
Grounded
theory
analysis of
semistructured
interview
transcripts.
Interview
transcripts
with eight
qualified
clinical
psychologists
Relationship
between
researcher and
participants not
adequately
considered.
Potential
sampling bias,
individuals
volunteered,
response rate
not clear.
Spirituality as an elusive concept,
avoided in clinical psychology due to
cultural unease, personal irrelevance
and lack of familiarity with appropriate
language.
Participants aimed to understand and
respect client beliefs and to suspend
judgment. This became difficult when
beliefs were contributing to distress.
They would then disengage from the
beliefs, seek understanding that
reduces distress but fits with beliefs, or
refer on to a religious leader.
Harbidge, P. R. (2015).
An exploration of how
clinical psychologists
make sense of the
roles of religion and
spirituality in their
clinical work with
adults who have
experienced trauma
(Doctoral dissertation).
Retrieved from British
Library e-thesis online
service
(uk.bl.ethos.667987).
7/8
To explore: How
clinical
psychologists
define and
understand their
own values with
regard to
religion and
spirituality. The
role of religion
and spirituality
within clinical
psychologists’
therapeutic
work with adults
who
have
experienced
trauma.
Qualitative
study.
Thematic
analysis of
transcripts of
semistructured
interviews.
Interview
transcripts
with eight
qualified
clinical
psychologists
with
experience of
working with
trauma.
Recruitment
methods are not
clearly stated.
Researcher
acknowledges
that her identity
as a Christian
may impact the
interviews and
analysis. All
female sample.
Participants felt more connected with
spirituality than religion. They found
these topics difficult to discuss and
their talk contained contradictions. The
influence of personal experiences and
psychological theory was noted.
Participants felt there was a lack of
psychological theory beyond religion
as symbolic or a psychological
defence. Wider contexts: NHS time
constraints, the medical model,
radicalisation and terrorism all
influence practice. Trauma: Theoretical
definition versus subjective
experience. Religion as an anchor in
extreme distress and central to
meaning making, which can be helpful
or can increase distress.
Aim to be curious, to value client’s
beliefs, and to notice difference.

SPIRITUALITY IN CLINICAL PSYCHOLOGY 15
However, participants could give few
examples of working with these topics.
Malins, S. (2011).
Clinical psychologists'
experiences of
addressing spiritual
issues in supervision:
An interpretative
phenomenological
analysis (Doctoral
dissertation).
Retrieved from British
Library e-thesis online
service
(uk.bl.ethos.580379)
6/8
To explore how
clinical
psychologists
address spiritual
issues in
supervision.
Qualitative
study.
Interpretive
phenomenolo
gical analysis
on transcripts
of
semistructured
interviews.
Interview
transcripts
with seven
qualified
clinical
psychologists.
Recruitment
biased to those
who had
successfully
raised the topic
in supervision.
Impact of the
religious beliefs
of researcher
not considered.
The Ineffable Nature of Spirituality:
Spirituality as difficult to put into words
and hard to challenge.
Struggles with Spirituality: Tension
between exploring clients’ experiences
and psychological theory. Caution
about revealing personal views due to
potential judgment from colleagues.
Negotiating Struggles: Recognising
what they do get from supervision and
that risk has to be a priority.
Substituting acceptable terms such as
existential questions or death anxiety
for spiritual or religious terms.

SPIRITUALITY IN CLINICAL PSYCHOLOGY 16
Mills, J. (2010). An
exploration of trainee
clinical psychologists'
experiences of
engaging with psycho
spiritual issues in
clinical practice
(Doctoral dissertation).
Retrieved from British
Library e-thesis online
service
(uk.bl.ethos.522435)
6/8
To explore trainee
psychologist’s
experience of
engaging with
psycho spiritual
constructs in
clinical practice.
Questionnair
es sent to
clinical
psychology
course staff,
asking about
provision of
training on
spirituality.
Interviews
with third
year trainees.
12 courses
responded to
questionnaire
asking about
training
provision
Eight
individual
interviews
asking about
experiences.
Sample bias.
75% described
themselves as
religious. Lack
of
consideration
of the impact
of researcher’s
own faith on
interviews or
analysis. All
female sample.
Range of teaching reported: 0-2.5 days
(25% = 0).
Provision of training on religion and
spirituality was seen as inadequate.
Scientist practitioner model viewed as
reducing openness to spiritual ideas.
Personal history and training were
recognised as impacting practice.
Existential issues: dilemmas arose
around life and death issues, which
participants felt unprepared to discuss.
Locus of control: Internal barriers: fear
of compromising the therapeutic
relationship through bias, ignorance,
invested interest & personal disclosure.
External barriers: NHS philosophies;
socio-political views; lack of training or
professional guidelines, psychology’s
lack of clarity on including religion and
spirituality into clinical practice.
Personal beliefs as causing tension
around disclosure, confidentiality, bias,
assumptions and causing offence.

SPIRITUALITY IN CLINICAL PSYCHOLOGY 17
Mulla, A. (2012). How
British NHS Clinical
Psychologists talk
about their experiences
of considering
spirituality in
therapeutic sessions
(Doctoral dissertation).
Retrieved from British
Library e-thesis online
service
(uk.bl.ethos.542399 )
5/8
How do clinical
psychologists talk
about their
experiences of
dealing with
spirituality in
therapeutic
sessions, the
clinical skills
required and how
these skills
develop?
Qualitative
study.
Grounded
theory
analysis of
interview
transcripts.
Interviews
with 12
qualified
clinical
psychologists
working in the
NHS.
Lack of clarity
about how the
final
participants
were recruited.
Researcher
acknowledges
the impact of
her Muslim faith
and dress on
the interviews
and analysis.
Including people's spiritual beliefs was
seen to improve engagement and
outcome. Tolerance, open discussion
and better training were desired.
Competence as based on experience,
knowledge, confidence and training.
Negative staff reactions to discussing
spirituality were reported, resulting in
avoidance in discussions or training.
Religion as a ‘luxury topic’ and not a
priority, particularly in supervision.
Spirituality located in the otherness of
patients, including race.
Myers, J. & Baker, M.
(1998). Religiously
committed clinical
psychologists, talking.
Clinical Psychology
Forum, 117, 30-32.
4/8
Not clearly stated.
Qualitative
study.
Grounded
theory
analysis of
interview
transcripts.
Interviews
with 5
religiously
committed
NHS clinical
psychologists.
Recruitment
methods not
clear. All
female
sample.
Lack of clarity
in aims of the
research. No
consideration
of the impact of
the researcher
on the
research.
Capabilities of religious psychologists:
Attunement to client (religious) issues.
Religious understanding could inform
assessment and intervention.
Professional self-care: linking with the
infinite and energising work.
Serious inattention paid to the religious
dimension: Neglect of client’s religious
concerns by secular colleagues,
negative talk towards religion in the
workplace. Concerns not shared as
expected them to be dismissed.
Psychological theory and training were
seen to overlook religion, perpetuating
neglect.

SPIRITUALITY IN CLINICAL PSYCHOLOGY 18
Read, R., Moberly, N.
J., Salter, D., &
Broome, M. R. (2016).
Concepts of mental
disorders in trainee
clinical psychologists.
Clinical Psychology
and Psychotherapy.
DOI:
10.1002/cpp.2013
N/A
To explore the
attitudes of
trainee clinical
psychologists
towards mental
disorders.
Online
questionnaire.
Quantitative
analysis.
Maudsley
Attitude
Questionnair
e. (MAQ)
Responses
on a Likert
scale. 289
respondents.
Not clear what
proportion of
those invited to
take part
responded to
the
questionnaire.
Acknowledges
that the MAQ
has not been
validated with a
clinical
psychology
sample.
The hierarchy of model endorsement
(from most to least) was: social realist,
social constructionist, cognitive,
psychodynamic, behavioural,
biological, nihilist and spiritual [with the
mean score for spiritual falling between
disagree and strongly disagree across
all four components for all four
diagnoses].
Psychologists endorsed the spiritual
model more strongly than psychiatrists
for schizophrenia but not for the other
diagnostic categories.
A significant association between
religion and a “psychodynamic–
spiritual” dimension was found. The
atheist group had a significantly lower
average score on the
psychodynamicspiritual dimension than
the Christian, agnostic and no religion
groups.
SPIRITUALITY IN CLINICAL PSYCHOLOGY 19
Smiley, T. (2001a).
Non-religious
psychologists talking:
What happens when a
psychologist who is not
committed to any
religion encounters
religious beliefs from
clients? (Unpublished
qualitative research
project). Retrieved
from British Library
ethesis online service
(uk.bl.ethos.699806)
5/8
To explore what
happens when a
psychologist who
is not committed
to a particular
religion
encounters
religious beliefs
from clients.
Qualitative
study.
Interpretive
phenomenolo
gical analysis
on interview
transcripts.
Interviews
with six
psychologists
(five clinical,
one
counselling)
without
religious
affiliation or
belief.
Impact of the
researcher on
the process of
research is not
considered.
Recruitment
process and
sample
population not
clear.
Dominant theme was the difference
between therapist and client beliefs,
particularly ignorance about client
beliefs, which was seen as potentially
positive or negative, and disagreement
with client beliefs, which was primarily
seen as harmful to engagement.
Including religion in clinical work was
rare. When raised most said it might be
in the formulation but less agreement
on inclusion in intervention planning. All
discussed potential negative impacts of
religion, five of six discussed potential
positive impacts.
Smiley, T. (2001b).
Clinical psychology
and religion: A survey
of the attitudes and
practices of clinical
psychologists in South
East England
(Doctoral dissertation).
Retrieved from British
Library e-thesis online
service
(uk.bl.ethos.699806)
N/A
Survey the
religious
orientations and
attitudes of a
population of
clinical
psychologists and
their experience
of, and approach
to, religion in the
clinical setting.
Descriptive
statistics.
Comparisons
between
different
groups and
with research
carried out in
the USA.
Developed a
survey based
on past
research.
Sent by post
to clinical
psychologists
working in the
South
Thames
Region. 246
responses.
Likely bias in
those taking
the time to
respond. Use
of a scale
developed for
the research
rather than
validated or
previously used
tools.
62% of respondents did not identify
with a religion. 52% reported
nontraditional forms of spirituality
(NTS) as important in their lives. 68%
indicated religious affiliation or value of
NTS. 56% say therapy can be
conducted independent of
metaphysical beliefs. 73% disagreed
that therapy is more helpful when
beliefs are shared. 76% of
respondents felt it was often or always
appropriate to consider client religious
values, but only 36% felt it was
appropriate to often or always ask
about them at assessment.
The most frequently reported religious
issues were existential (19%).
Religious psychologists were more
likely to report that their orientation
influences and enhances clinical work.

Running head: SPIRITUALITY IN CLINICAL PSYCHOLOGY
Findings
A summary of the 13 studies included for review is presented in
Table 1. The majority of the research utilized qualitative methods, with
only two papers following a quantitative design. Eleven studies
conducted interviews with CPs, analysed using: grounded theory (six
papers), IPA (four papers) or thematic analysis (one paper). Nine
studies were conducted with qualified psychologists, two with trainees.
Two focused on particular areas of work, trauma (Harbidge, 2015), and
psychosis (Arshad, 2007). Four identified participants based on their
beliefs: no religion (Smiley, 2001a), Muslim (Betteridge, 2012) or
Christian (Baker & Wang, 2004; Myers & Baker, 1998). One paper
selected participants who had raised spirituality in supervision (Malins,
2011).
The quantitative studies administered questionnaires to CPs. One
was developed specifically for the study in question based on prior
research (Smiley, 2001b) and administered by post to CPs working in
South East England. The other delivered the Maudsley Attitude
Questionnaire (MAQ) to clinical psychology trainees online. Smiley
(2001b) found that although the majority (62%) of respondents did not
identify with a religion, a minority could be considered “strongly
religious” (18%), and 52% valued non-traditional forms of spirituality.
Although roughly similar proportions of religious and non-religious
psychologists believed that therapy can be offered without the influence
of one’s metaphysical beliefs (an average of 56%), more religious

psychologists reported that their beliefs impact on, and enhance, their
practice. A strong majority (76%) felt it was appropriate to consider client
religious values, but only 36% felt it was appropriate to routinely ask
about them at assessment. When asked to provide examples of the
sorts of religious issues clients bring to therapy, the most common
category was existential issues (19% of responses), although there was
variation depending on specialism.
The MAQ was developed to assess trainee psychiatrists’ concepts
of mental illness (Harland et al., 2009). It examines eight conceptual
models (biological, cognitive, behavioural, psychodynamic, social realist,
social constructionist, nihilist, spiritual) across the domains of aetiology,
classification, research and treatment, for four diagnoses. Read et al.
(2016) found that trainee psychologists endorse the spiritual model for
schizophrenia more than trainee psychiatrists, although the spiritual
model was the least endorsed overall. Three components were
identified which accounted for 57.54% of the variance of the aggregated
attitude scores, loading psychodynamic and spiritual understandings
onto one dimension. Individuals identifying as atheists were less likely
than their peers to endorse this understanding of mental health
diagnoses.
The aims of the studies were all exploratory, looking to investigate
how religious or spiritual topics are conceptualized, addressed in clinical
practice, and/or raised in supervision. The impact of personal beliefs on
this process was included for seven studies (Arshad, 2007; Baker &

Wang, 2004; Begum, 2012; Betteridge, 2012; Harbidge, 2015; Read et
al., 2016; Smiley, 2001b).
There were several themes which occurred consistently across
most qualitative studies. These included participants reporting
insufficient training, theory and/or guidance on addressing spiritual
issues in clinical practice
(Arshad, 2007; Baker & Wang, 2004; Harbidge, 2015; Malins, 2011;
Mills, 2010; Mulla, 2012; Myers & Baker, 1998). Spirituality was
described as hard to discuss and to put into language (Begum, 2012;
Crossley & Salter, 2005; Harbidge, 2015; Malins, 2011) and in line with
the BPS code of ethics and conduct (BPS, 2009) the importance of
maintaining a curious, open therapeutic stance which respects and
addresses differences in beliefs was emphasized (Arshad, 2007;
Betteridge, 2012; Crossley & Salter, 2005; Harbidge, 2015; Malins,
2011). However, in Harbidge (2015) it was noted that although these
therapeutic aims were widely endorsed, when requested, few examples
of engaging with spirituality in practice were forthcoming.
The impact of wider context was also noted across several studies.
NHS culture and time constraints of public sector work were seen as
limiting what can be discussed, and spirituality was reported to be a
secondary, ‘luxury’ topic (Betteridge, 2012; Harbidge, 2015; Malins,
2011; Mills, 2010; Mulla, 2012). The scientist-practitioner model
espoused by clinical psychology was considered to be at odds with
openness to spiritual ideas in two studies (Begum, 2012; Mills, 2010).

A reluctance to disclose one’s own position to colleagues or clients
was also reported in several studies (Baker & Wang, 2004; Betteridge,
2012; Malins, 2011; Mills, 2010). This may link to the wider social
discomfort around these topics which was identified (Betteridge, 2012;
Crossley & Salter, 2005; Harbidge, 2015), and to individuals’
expectation of negative reactions from colleagues (Baker & Wang,
2004; Betteridge, 2012; Malins, 2011; Mulla, 2012; Myers & Baker,
1998). Three of the five studies where negative colleague reactions
were reported or anticipated were those which specifically interviewed
religious CPs. It may be that the experience of being a religious
psychologist working in the NHS increases the expectation of a hostile
response. As Malins
(2011) and Mulla (2012) did not report the levels of religiosity in their samples,
it is not possible to examine its impact. The sense of risk in discussing these
topics in a work setting contrasts with Harbidge’s (2015) report that participants
talked about these topics lightly. This difference may partially be due to the
majority of Harbidge’s sample having no religious affiliation.
Participants in qualitative studies that specifically recruited
religious individuals viewed their religiosity as enhancing their ability to
engage with spirituality, and bolstering personal resilience at work
(Baker & Wang, 2004; Betteridge, 2012; Myers & Baker, 1998). This is
consistent with Smiley’s (2001b) finding that a greater proportion of
religious individuals than nonreligious individuals, reported that their
beliefs enhanced clinical practice.

Beyond these core themes, disparate findings were reported
across the studies, in part reflecting variations in the research questions
investigated and methods of analysis. The influence of past experiences
on current practice was recognised (Begum, 2012; Harbidge, 2015;
Mills, 2010), and participants described feeling more comfortable with
spirituality than religion (Begum, 2012; Harbidge, 2015). An increased
sense of difficulty was reported when aspects of clients’ beliefs were
disagreed with (Smiley, 2001a) or appeared to contribute to client
distress (Crossley & Salter, 2005). Some studies reported an
acknowledgement that religion can be either helpful or detrimental
depending on the meanings made and how religious beliefs relate to
negative experiences (Crossley & Salter, 2005; Harbidge, 2015; Smiley,
2001a).
One study reported that participants aimed to challenge unhelpful
religious beliefs, but saw this area as ‘hard work’ (Arshad, 2007).
Trainees in Mill’s (2010) study reported fearing being seen as biased or
ignorant, and that their lack of expertise may damage the therapeutic
relationship. Similarly, Smiley’s (2001a) non-religious psychologists
spoke of their ignorance regarding religious issues. Two studies
reported that these topics may be rephrased in order to be acceptable in
clinical settings, such as referring to ‘existential issues’ or ‘values’
(Begum, 2012; Malins, 2011). Mulla (2012) noted that her participants
distanced themselves from religion, viewing it as ‘other’.

Discussion
This review covered thirteen papers, eleven qualitative interview
studies and two quantitative questionnaire studies. Psychologists taking
part in the research tended to report a lack of training and guidance in
this area, and discomfort with the topic. Overall, religiously committed
individuals are more likely to view their beliefs as positively influencing
their practice, and report reluctance to disclose these beliefs at work.
Trainee psychologists do not endorse a spiritual understanding of
mental illness, but are less opposed to this than psychiatry trainees.
NHS culture, societal attitudes and the scientistpractitioner model were
all reported as constraining the profession’s engagement with these
topics. The importance of maintaining a curious and open stance which
respects clients’ beliefs and addresses difference in therapy was also
highlighted.
A notable limitation of this review is the high proportion of
unpublished doctoral theses included. Whilst including unpublished
studies in a systematic review when eligible and appropriate can help to
minimise publication bias (Higgins & Green, 2011), it can introduce other
biases. For example, researchers may be more reluctant to share
unpublished studies with no significant results, and unpublished studies
may be poorer quality than published studies (Egger, Jüni, Bartlett,
Holenstein, & Sterne, 2003), although this has been disputed (Hopewell,
2004). The absence of peer review which can call unpublished studies
into question (Higgins & Green, 2011), is less relevant for the studies

included here, as they have been examined at doctoral level. Whilst
most of the unpublished studies scored reasonably on the CASP, scores
on rating scales are themselves prone to bias (Petticrew & Roberts,
2006).
A further limitation of this review is the lack of availability of a
second researcher to assess the eligibility of a portion of search results
for inclusion. Similarly due to a lack of resources, inherent in
undertaking a review as part of a doctoral research project, it was not
possible to include a second rater to check the assessment of study
quality.
The lack of publication may indicate that this area is not a priority
for clinical psychology, or may be an artefact of the context in which the
research was generated, as many doctoral theses are not submitted for
publication. The research reviewed spans two decades; this has
increased over the last five years, with almost half the studies being
carried out in that time. This suggests interest in these areas is
increasing. A lack of training and guidance was raised in even the most
recent qualitative research (Harbidge, 2015), indicating that the lack of
publication has resulted in poor dissemination of the results and minimal
impact on training.
All of the studies were undertaken as part of doctoral training. This
may have made themes related to training quality particularly salient.
Similarly, of the twelve authors, nine have their own religious faith (six
Christians and three

Muslims), and two reported religious heritage but current non-practice
(one
Jewish, one Muslim). Only for one study was the spiritual background of
the researcher not discernable. The religious beliefs of the researchers
may introduce bias at various stages. It may affect the choice of
research question or methodology. For qualitative research, it may
influence the interview schedule, as well as impacting on analysis and
the salience of different themes. In some studies the potential influence
of the researcher on the interviews or on the development of themes
during analysis was acknowledged. Attempts to address this were made
in some studies, for example, by making possible concerns explicit in
the interview, or asking supervisors and non-religious peers to check
qualitative analysis.
As all of the studies relied on individuals volunteering to take part,
the participants were more likely to be interested in, or have strong
views about, spirituality. This is the case for all except Read et al.
(2016), which did not focus solely on spirituality. The extent of this bias
could not be fully assessed across all studies as several did not report
the proportion of the total population that took part.
One author acknowledged that, because the topic was
uncomfortable, people talked generally rather than about their personal
experiences, making IPA less appropriate as a method of analysis. This
discomfort may have introduced a bias across the qualitative papers,
with participants potentially speaking in abstract and politically correct
ways.

The literature reviewed above has all been based on either
questionnaire or individual interview data. It could be argued that
research has failed to attend to the social aspect of decision making and
influence of professional training, culture, and colleagues on values and
practice (Goffman, 1986). Future research should examine the impact of
professional discourses and group dynamics on how these topics may,
or may not, be addressed in training cohorts and staff teams. As it is
designed and delivered, the impact of training on staff and clients should
be studied, with training modified and reassessed on the basis of the
findings.
Questionnaire research has looked at attitudes in the South East
of England. It would be helpful for this to be repeated in other areas of
the UK to see whether responses differ. Building on the consistent
report of a lack of training in this area, future research could examine
the effectiveness and acceptability of proposed training methods or
models across trainee or qualified psychologists.
Conclusion
A relatively small number of studies have been conducted in the
UK exploring the attitudes, beliefs and practices of CPs in relation to
spirituality. Some CPs are religiously committed and view their faith as
enhancing their clinical practice. However, population studies suggest
that the majority are not religiously affiliated and believe their practice to
be value free. Most studies find that psychologists describe these topics
as difficult and report insufficient

training and guidance.
References
Arshad, R. (2007). How do clinical psychologists work with religious
themes in psychosis? (Doctoral dissertation). Retrieved from
British Library e-thesis online service (uk.bl.ethos.697398).
Baker, M. & Wang, M. (2004). Examining connections between values
and practice in religiously committed U.K. clinical psychologists.
Journal of Psychology and Theology, 32(2), 126-136.
Begum, N. (2012). Trainee clinical psychologists talking about religion
and spirituality in their work (Doctoral dissertation). Retrieved from
British Library e-thesis online service (uk.bl.ethos. 575830).
Bergin, A. E. & Jensen, J. P. (1990). Religiosity of psychotherapists: A
national survey. Psychotherapy: Theory, Research, Practice,
Training, 27, 3-7.
Betteridge, S. (2012). Exploring the clinical experiences of Muslim
psychologists in the UK when working with religion in therapy
(Doctoral dissertation).
Retrieved from British Library e-thesis online service
(uk.bl.ethos.637577).
Bilgrave D. P. & Deluty, R. H. (1998). Religious beliefs and therapeutic
orientations of clinical and counselling psychologists. Journal for
the Scientific Study of Religion, 37, 329-349.
Bosworth, H. B., Park. H-S., McQuoid, D. R., Hays, J. C., & Steffens,
D.C. (2003). The impact of religious practice and religious coping

on geriatric depression. International Journal of Geriatric
Psychiatry, 18, 905–914.
British Psychological Society (2009). Code of ethics and conduct.
Leicester:
British Psychology Society.
British Psychological Society (2011).Good practice guidelines on the use
of psychological formulation. Leicester: British Psychology Society.
Bussema, K. E. & Bussema, E. F. (2000). Is there a balm in Gilead? The
implications of faith in coping with a psychiatric disability.
Psychiatric Rehabilitation Journal, 24, 117–124.
Campbell, C. D. (2011). APA accreditation of doctoral psychology
programs in
Christian universities. Journal of Psychology & Theology, 39(1),
59-67.
Capps, D. (1992). Religion and child abuse: Perfect together. Journal for
the
Scientific Study of Religion, 31, 1-14.
Commission for Healthcare Audit and Inspection (2007). Caring for dignity.
A national report on dignity in care for older people while in hospital.
London:
Healthcare Commission.
Critical Appraisal Skills Programme (2013). Qualitative research
checklist.
Retrieved from http://www.casp-uk.net/casp-tools-checklists
Crossley, J. P. & Salter, D. P. (2005). A question of finding harmony: A
grounded theory study of clinical psychologists’ experience of

addressing spiritual beliefs in therapy. Psychology and
Psychotherapy: Theory, Research and Practice, 78, 295–313.
Department of Health. (2009). Religion or belief: A practical guide for the
NHS.
London: Department of Health.
Egger, M., Jüni, P., Bartlett, C., Holenstein, F., & Sterne, J. (2003). How
important are comprehensive literature searches and the
assessment of trial quality in systematic reviews? Empirical study.
Health Technology
Assessment, 7, 1-76.
Ellis, M. R., Vinson, D. C., & Ewigman, B. (1999). Addressing spiritual
concerns of patients: family physicians’ attitudes and practices.
Journal of Family Practice, 48, 105–109.
Exline, J. J. (2002). Stumbling blocks on the religious road: Fractured
relationships, nagging vices, and the inner struggle to believe.
Psychological Inquiry, 13, 182-189.
Exline, J. J., Yali, A. M., & Lobel, M. (1999). When God disappoints:
Difficulty forgiving God and its role in negative emotion. Journal of
Health Psychology, 4, 365–379.
Exline, J. J., Yali, A. M., & Sanderson, W. C. (2000). Guilt, discord, and
alienation: The role of religious strain in depression and suicidality.
Journal of Clinical Psychology, 56, 1481–1496.

Fitchett, G., Burton, L. A., & Sivan, A. B. (1997). The religious needs and
resources of psychiatric inpatients. Journal of Nervous and Mental
Disease, 185, 320–326.
Flynn, P. M., Joe, G. W., Broome, K. M., Simpson, D. D., & Brown, B. S.
(2003). Looking back on cocaine dependence: Reasons for
recovery. The American Journal on Addictions, 12, 398-411.
Gartner, J., Harmatz, M., Hohmann, A., Larson, D., & Gartner, A. F.
(1990). The effect of patient and clinician ideology on clinical
judgment: A study of ideological countertransference.
Psychotherapy: Theory, Research, Practice, Training, 27, 98-106.
Goffman, E. (1986). Frame analysis: An essay on the organization of
experience.
Boston: North-Eastern University Press.
Hathaway, W. L., Scott, S. Y., & Garver, S. A. (2004). Assessing
religious/spiritual functioning: A neglected domain in clinical
practice?
Professional Psychology: Research and Practice, 35, 97-104.
Harbidge, P. R. (2015). An exploration of how clinical psychologists make
sense of the roles of religion and spirituality in their clinical work
with adults who have experienced trauma (Doctoral dissertation).
Retrieved from British Library e-thesis online service
(uk.bl.ethos.667987).
Harland, R., Antonova, E., Owen, G. S., Broome, M., Landau, S., Deeley,
Q., &

Murray, R. (2009). A study of psychiatrists' concepts of mental
illness.
Psychological medicine, 39, 967-976.
Health Professions Council (2008). Standards of conduct, performance
and ethics. London: Health Professions Council.
Hebert, R., Zdaniuk, B., Schulz, R., & Scheier, M. (2009). Positive and
negative religious coping and well-being in women with breast
cancer. Journal of Palliative Medicine, 12, 537-545.
Hefti, R. (2011). Integrating religion and spirituality into mental health
care, psychiatry and psychotherapy. Religions, 2, 611-627.
Higgins, J. P. T. & Green, S. (Eds.), (2011). Cochrane handbook for
systematic reviews of interventions. The Cochrane Collaboration.
Retrieved from: www.handbook.cochrane.org.
Hopewell, S. (2004). Impact of grey literature on systematic reviews of
randomized trials (Doctoral dissertation). University of Oxford.
Huguelet, P. & Koenig, H. G. (2009). Religion and spirituality in psychiatry.
Cambridge: Cambridge University Press. Retrieved from:
http://dx.doi.org/10.1017/CBO9780511576843.001
Huguelet, P., Mohr, S., Borras, L., Gillieron, C., & Brandt, P. Y. (2006).
Spirituality and religious practices among outpatients with
schizophrenia and their clinicians. Psychiatric Services, 57, 366-
372.

Ipsos MORI (2007). Survey on beliefs. Retrieved from:
https://www.ipsosmori.com/researchpublications/researcharchive/2
46/Survey-on-
Beliefs.aspx
Koenig, H. G., Bearon, L. B., & Dayringer, R. (1989). Physician
perspectives on the role of religion in the physician-older patient
relationship. Journal of Family Practice, 28, 441–448.
Larson, D. B. & Larson, S. S. (2003). Spirituality's potential relevance to
physical and emotional health: A brief review of quantitative
research. Journal of Psychology and Theology, 31(3), 37-51.
Lee, E. & Baumann, K. (2013). German psychiatrists’ observation and
interpretation of religiosity/spirituality. Evidence-Based
Complementary and Alternative Medicine. Article ID 280168, 8
pages http://dx.doi.org/10.1155/2013/280168
Malins, S. (2011). Clinical psychologists' experiences of addressing
spiritual issues in supervision: An interpretative phenomenological
analysis (Doctoral dissertation). Retrieved from British Library e-
thesis online service (uk.bl.ethos.580379).
Masters, K. S. (2010). Commentary: The role of religion in therapy: Time
for psychologists to have a little faith? Cognitive and Behavioural
Practice, 17, 393-400.
Mayers, C., Leavey, G., Vallianatou, C., & Barker, C. (2007). How clients
with religious or spiritual beliefs experience psychological help-

seeking and therapy: A qualitative study. Clinical Psychology and
Psychotherapy, 14, 317-327.
McClure, R. F, & Livingston, R. B. (2000). Religious values of counselors,
psychologist, and college students. Journal of Professional
Counseling, Practice, Theory, & Research, 28(2), 78-85.
Mental Health Foundation (2006). The impact of spirituality on mental
health: A review of the literature. London: Mental Health
Foundation.
Mills, J. (2010). An exploration of trainee clinical psychologists'
experiences of engaging with psycho spiritual issues in clinical
practice (Doctoral dissertation). Retrieved from British Library e-
thesis online service (uk.bl.ethos.522435).
Mitchell, J. R. & Baker, M. C. (2000). Religious commitment and the
construal of sources of help for emotional problems. British Journal
of Medical Psychology, 73, 289-301.
Moher, D., Liberati, A., Tetzlaff, J., & Altman, D. G. (2009). Preferred
reporting items for systematic reviews and meta-analyses: The
PRISMA statement.
PLoS Med, 6(6). DOI:10.1371/journal.pmed1000097
Mohr, S., Brandt, P., Borras, L., Gilliéron, C., & Huguelet, P. (2006).
Toward an integration of spirituality and religiousness into the
psychosocial dimension of schizophrenia. American Journal of
Psychiatry, 163, 1952–1959.

Mulla, A. (2012). How British NHS Clinical Psychologists talk about their
experiences of considering spirituality in therapeutic sessions
(Doctoral dissertation). Retrieved from British Library e-thesis online
service
(uk.bl.ethos.542399)
Myers, J. & Baker, M. (1998). Religiously committed clinical
psychologists, talking. Clinical Psychology Forum, 117, 30-32.
Office for National Statistics (2011). What does the Census tell us about
religion in 2011? Retrieved from:
http://webarchive.nationalarchives.gov.uk/20160105160709/http://
www.on
s.gov.uk/ons/rel/census/2011-census/detailed-characteristics-for-
localauthorities-in-england-and-wales/sty-religion.html
Office for National Statistics (2012). Religion in England and Wales 2011.
Retrieved from:
https://www.ons.gov.uk/peoplepopulationandcommunity/culturalide
ntity/reli gion/articles/religioninenglandandwales2011/2012-12-11
Oman, D. (2013). Defining religion and spirituality. In R. F. Paloutzian &
C. L.
Park (Eds.), Handbook of the psychology of religion and spirituality,
(pp.
23-47). London: Guildford Press.
Petticrew, M. & Roberts, H. (2006). Systematic reviews in the social
sciences.
Oxford: Blackwell.

Phillips, R. (2010). American millennials are spiritually diverse. Retrieved
from:
http://www.lifeway.com/Article/LifeWay-Research-finds-
Americanmillennials-are-spiritually-diverse
PRISMA: Welcome to the Preferred Reporting Items for Systematic
Reviews and
Meta-Analyses (PRISMA) website! (2015) Retrieved from:
http://www.prisma-statement.org/
Read, R., Moberly, N. J., Salter, D., & Broome, M. R. (2016). Concepts of
mental disorders in trainee clinical psychologists. Clinical
Psychology and
Psychotherapy. DOI: 10.1002/cpp.2013
Richards, P. S. & Bergin, A. E. (1997). A spiritual strategy for counseling
and psychotherapy. Washington DC: American Psychological
Association.
Royal College of Psychiatrists (2013). Recommendations for psychiatrists
on spirituality and religion: Position statement PS03/2013. London:
Royal
College of Psychiatrists. Retrieved from:
https://www.rcpsych.ac.uk/pdf/PS03_2013.pdf
Saucier, G. & Skrzypińska, K. (2006). Spiritual but not religious?
Evidence for two independent dispositions. Journal of Personality,
74, 1257-1292.

Shafranske, E. P. & Malony, H. N. (1990). Clinical psychologists' religious
and spiritual orientations and their practice of psychotherapy.
Psychotherapy:
Theory, Research, Practice, Training, 27(1), 72-78.
Smiley, T. (2001a). Non-religious psychologists talking: What happens
when a psychologist who is not committed to any religion
encounters religious beliefs from clients? (Unpublished qualitative
research project). Retrieved from British Library e-thesis online
service (uk.bl.ethos.699806).
Smiley, T. (2001b). Clinical psychology and religion: A survey of the
attitudes and practices of clinical psychologists in South East
England (Doctoral dissertation). Retrieved from British Library e-
thesis online service (uk.bl.ethos.699806).
United States Census Bureau, (2010). Self-described religious
identification of adult population. Retrieved from:
http://www.census.gov/library/publications/2009/compendia/statab/
129ed/ population.htm
YouGov (2014). Religion survey result. Retrieved from:
http://cdn.yougov.com/cumulus_uploads/document/xbqfnxhcct/YG-
Archive-140423-Religion.pdf
Zinnbauer, B. J. & Pargament, K. I. (2005). Religiousness and spirituality.
In R. Paloutzian & C. Park (Eds.), Handbook of the psychology of
religion and spirituality (pp.21-42). London: Guilford Press.

Zurlo, G. A. & Johnson, T. M. (2016). Unaffiliated, yet religious: A
methodological and demographic analysis. In R. Cipriani & F.
Garelli (Eds.) Sociology of Atheism (pp. 50-74). Boston: Brill.
Appendix A
Search Terms and Results
03/11/16 – Searched PubMed 2,804 Results
((Spiritual*[Title/Abstract] OR religio*[Title/Abstract] OR
faith[Title/Abstract] OR sacred[Title/Abstract]) OR
(Spiritual*[Supplementary Concept] OR religio*[Supplementary Concept]
OR faith[Supplementary Concept] OR sacred[Supplementary Concept])
OR (Spiritual* OR religio* OR faith OR sacred[MeSH Major Topic])) OR
(Spiritual*[MeSH Subheading] OR religio*[MeSH Subheading] OR
faith[MeSH Subheading] OR sacred[MeSH Subheading])) OR (Spiritual*
OR religio* OR faith OR sacred[MeSH Terms])) AND ((clinical
psycholog*[Title/Abstract]) OR (clinical
psycholog*[Supplementary Concept]) OR (clinical psycholog*[MeSH
Major Topic]) OR (clinical psycholog*[MeSH Subheading]) OR (clinical
psycholog*[MeSH Terms]))
04/11/16 – Searched PsychInfo Via open Athens HDAS 3,728 Results
Document title, abstract, identifier (keyword), Exact major subject
heading, Exact subject heading, subject heading, subject heading all,
word in major subject heading
1 Spiritual*
2 religio*
3 faith
4 sacred
5 clinical psycholog*

6 1 OR 2 OR 3 OR 4
7 6 AND 5
13/12/2016 – Searched Web of knowledge 94 results
TS=((Spiritual* OR religio* OR faith OR sacred) AND “clinical
psycholog*”)
Appendix B CASP Qualitative Research Checklist
(CASP, 2013)
Item
Question
1
Was the research design appropriate to address the aims of the research?
2
Was the recruitment strategy appropriate to the aims of the research?
3
Was the data collected in a way that addressed the research issue?
4
Has the relationship between researcher and participants been adequately
considered?
5
Have ethical issues been taken into consideration?
6
Was the data analysis sufficiently rigorous?
7
Is there a clear statement of findings?
8
Is the research valuable?
SCHOOL OF PSYCHOLOGY
DOCTORATE IN CLINICAL PSYCHOLOGY
EMPIRICAL PAPER

What Can and Cannot be Said: Discourses of Spirituality and Religion
in
Clinical Psychology
Trainee Name: Elizabeth Challis
Primary Research Supervisor: Dr Janet Smithson
Senior Lecturer, University of Exeter
Secondary Research Supervisor: Professor Ed Watkins
Professor of Experimental and
Applied
Clinical Psychology/Director of
Research for
Professional Doctorates
Target Journal: Qualitative Health Research
Word Count: 7,995 words (excluding abstract, table of
contents, list of figures, references,
footnotes, appendices)
Submitted in partial fulfilment of requirements for the Doctorate Degree
in Clinical Psychology, University of Exeter
Abstract
Objective: To examine the discourses used by trainee and qualified
clinical psychologists from the South West of England to manage
discussions of spirituality and religion as they relate to clinical practice.

Methods: Four focus groups were carried out with a total of 25 qualified
and trainee clinical psychologists.Transcripts were analysed using
discourse analysis.
Results: Three key discourses were identified, giving insight into how
cohorts of qualified and trainee clinical psychologists manage
discussions of these difficult topics. These were: balancing medical and
therapeutic discourses, particularly when discussing psychosis and
religious or spiritual beliefs; positioning and the Other, including religion
and spirituality as a proxy for talking about race; and negotiating what
can or cannot be said, principally when sharing personal views.
Conclusion: Ensuring that clinical psychologists have an awareness of
the different discourses in use within the profession and how these may
impact practice is important. Explicit discussion of the medical and
therapeutic discourses likely to arise across different settings should be
encouraged, including how these can constrain discussions around
difficult topics such as spirituality and religion, race, and sexuality.
Training should equip psychologists to have an awareness of othering,
particularly in relation to religion or spirituality and race, and the
potential effects this could have on power and engagement in therapy
and broader work.
Keywords: Discourse Analysis, Spirituality, Religion, Culturally Sensitive
Practice, Clinical Psychology
Introduction

Spirituality and Clinical Psychology
Over a decade ago the Mental Health Foundation (MHF, 2006)
reviewed the literature examining the impact of spirituality on mental
health, and recommended that spiritual and religious needs routinely be
discussed with service users in mental health settings. However,
qualified clinical psychologists (CPs), and trainees (TCPs) report a lack
of training and guidance on addressing spiritual and/or religious material
in clinical practice (Arshad, 2007; Baker &
Wang, 2004; Harbidge, 2015; Malins, 2011; Mills, 2010; Mulla, 2012;
Myers & Baker, 1998). While national guidelines for including spirituality
and religion into healthcare are available (Commission for Healthcare
Audit and Inspection, 2007; Department of Health [DoH], 2009), their
primary focus is physical health services. The British Psychological
Society (BPS) only broadly acknowledges that religious diversity should
be recognised and respected in ethical conduct and psychological
formulations (BPS, 2009; 2011).
An apparent ‘discomfort’ between UK clinical psychology and
religion has been noted (Peden, 2012), supported by research in which
CPs and TCPs report difficulty discussing spirituality and religion
(Begum, 2012; Crossley & Salter, 2005; Harbidge, 2015; Malins, 2011).
This difficulty likely impacts training provision, guideline development
and reflection by individuals and teams. Given national documents
promoting discussion of spirituality and religion in mental health
services, the perceived lack of training and guidance, and that clinician

attitudes impact clinical decision making (Gartner, Harmatz, Hohmann,
Larson, & Gartner, 1990), clinical psychology as a profession needs to
better engage with these topics. This is key as they may influence
engagement, from both clinician and client, which in turn has been
shown to impact therapeutic outcomes (Horvath, 2001).
The current literature on clinical psychology, spirituality and religion
is based almost exclusively on interview data (e.g., Harbidge, 2015;
Malins, 2011; Mills, 2010;Mulla, 2012). However, practice is constrained
and shaped by professional roles, training, and the expectations of
colleagues (Goffman, 1986). Individuals’ responses vary depending on
context, who is addressed and how one is positioned in relation to them
(Billig, 1988; Willig, 2000). What individuals say during interviews with
researchers who are investigating this area, may therefore differ from
the normative professional discourses that exist in wider professional
training and work contexts.
This study builds on previous research on the attitudes of
individual psychologists by conducting focus groups with professional
colleagues to see how they negotiate these controversial topics.
Although not a natural setting, focus groups can provide access to a
population within its social context (Hoppe, Wells, Wilsdon, Gilmore, &
Morrison, 1994; Kitzinger, 1994). Analysis looking at what strategies and
discourses are used in discussing spirituality and religion can inform the
design and delivery of future training. As prior research has particularly
identified a reluctance to disclose one’s own beliefs to colleagues

(Baker & Wang, 2004; Betteridge, 2012; Malins, 2011; Mills, 2010)
attending to examples of where and how this reluctance is overcome (if
at all) may be particularly useful.
Focus Groups and Discourse Analysis
Focus groups produce interactive data which allow for the
negotiation and construction of meaning to be studied (Wilkinson, 1998)
and public discourses examined (Smithson, 2000). Focus groups can
be particularly useful for identifying obstacles preventing adherence to
guidance, or limiting behaviour modification (Wilkinson, 1998). This is
relevant to the discussion of spirituality and religion, which is
recommended (DoH, 2009; MHF, 2006) but uncomfortable for CPs
(Peden, 2012).
Discourse analysis (DA) views language as performing social
actions like persuasion, entertainment, blame or justification, rather than
expressing stable internal states such as attitudes or opinions (Potter &
Wiggins, 2007). It is more than a method of analysis, encapsulating a
social constructionist or critical realist epistemology (Billig, 1997), and
recognising the role discursive practices play in constructing, rather than
simply describing, reality. It is supported by research demonstrating that
people express different views in different settings (Billig, 1988), and
that power and position are (re)negotiated and maintained using
discursive practices (van Dijk, 1993). A glossary of key DA terms used in
this study is provided in Appendix A.

When studying individuals within professional and institutional
settings discourse is a key domain for research (Edwards & Potter,
2001). Positioning theory (Davies & Harré, 1990) is one aspect of DA
which examines what an individual may or may not do or say within a
professional context; how their positions and subsequent actions are
constrained (Harré, Moghaddam, Cairnie,
Rothbart, & Sabat, 2009). It asks: “Who speaks? In whose name do
they speak? Who do they address? Who do they speak for?” (Georgaca
& Avdi, 2011, p. 155). The ways individuals and groups position
themselves, each other, and the clients they serve will define how CPs
practice.
Attending to the detail of focus group talk, participants’ rhetorical
strategies and discursive agendas, is key when the topic is sensitive or
potentially inflammatory, and individuals risk accusations of prejudice,
bias or unprofessionalism (Potter & Wetherell, 1988). Individuals may
speak to forestall argument or portray an utterance as objective, rather
than opinion or evaluation (Jørgensen & Phillips, 2002).
This study expands the existing literature by examining the
discursive strategies which may impact the construction of professional
discourses in this area. Where past research has looked only at
interview or survey data, and has not considered discursive influences,
the use of DA and focus groups in this study allows for the interactions
between CPs and TCPs to be explored.

This study aims to answer the following research question: What
discourses do TCPs and CPs from South West England use to manage
discussions of spirituality and religion as they relate to clinical practice?
Method
Participants
Trainee and qualified psychologists from Exeter University and
Somerset Partnership NHS Foundation Trust were approached to
participate in focus groups between October 2016 and January 2017.
First year trainees were excluded as at this time they had minimal
clinical experience on training. All second and third year trainees were
approached to participate. To facilitate open discussion the focus groups
were carried out as professional cohorts. Trainees were not in focus
groups with qualified psychologists; second and third year trainees were
in separate groups. Qualified groups were planned within specialisms.
Potential participants were contacted by email with a brief
description of the study and participant information sheet (Appendix B).
They were invited to ask questions and express interest via email.
Trainee psychologists were also approached as a cohort to request
participation, particularly of those with little interest in religious or
spiritual matters.
Participants were not asked explicitly about demographic
categories such as ethnicity, gender or religious affiliation. DA
acknowledges that the context of how, where and by whom people are
addressed will influence how they respond or the positions they take up.

Asking for demographic information via a questionnaire or at the start of
the focus groups would set a particular context, and may have
constrained the positions which individuals felt were available to them in
subsequent discussions. Not asking participants to choose a particular
‘category’ for their religious or spiritual views also aimed to avoid unduly
influencing how I interacted with them and their discourses during
facilitation, transcription or analysis, based on how they had identified.
Four focus groups were carried out, three with trainees and one
with qualified psychologists. Of the 14 individuals in the second year of
training at Exeter, nine (64%) participated. Of the 13 trainees in year
three, 12 (92%) took part across two groups. The qualified focus group
included all four psychologists present at the bimonthly specialism
meeting. Overall 81% of those contacted agreed to participate.
Design
The study used a qualitative focus group design. DA methodology
was used to examine how professional cohorts discussed the inclusion
of spirituality and religion in clinical work.
Procedure
Ethical Approval. The study was approved by the University of Exeter
School of Psychology Ethics Committee and the Health Research
Authority (Appendix C). At the start of the focus group individuals were
asked to read the participant information (Appendix B) and opportunity
was given to ask questions. The voluntary nature of the research and
right to withdraw were emphasised. Participants were asked to respect

the confidentiality of other group members and the limits of
confidentiality for research carried out in a group setting were
highlighted. If happy to participate individuals then signed a consent
form (Appendix D). A debrief sheet (Appendix E) was provided after the
group.
Focus Group Schedule. A focus group schedule was developed
based on the existing literature, covering participants’ views on and
experience of talking about spiritual and religious matters with clients,
supervisors, and in training. A pilot interview was conducted with a Band
7 clinician from specialist psychological services. This identified possible
prompts, checked intelligibility and ensured flow of topics. It also served
as an opportunity for me to prepare for the role as researcher and group
facilitator. The resulting schedule (Appendix F) was applied flexibly to
maintain the flow of discussion as far as possible. Slight changes were
made to adapt the schedule for use with qualified staff (e.g. asking
about current practice as supervisors rather than future expectations).
The groups lasted between 45 and 70 minutes and were audiorecorded.
I transcribed each focus group within a week of completion using
Jefferson notation (Jefferson, 2004; see Appendix G). Completing
transcription prior to
the subsequent group aimed to increase recall of non-verbal
communication and aid with sections of poor sound quality.

Method of Analysis
The analysis was based on a discursive psychology approach, a
form of DA concerned with how psychological business is conducted in
talk. In particular, I focussed on how people attend to identities, attitudes
and cognitions (Potter & Wiggins, 2007). I also focussed on positioning
theory
(Davies & Harré, 1990), looking at how individuals’ discourses were
used to position themselves and others to construct relevant identities,
and participants’ discursive agendas (Georgaca & Avdi, 2011), the
rhetorical strategies individuals employed to manage and influence the
interaction. Although discourse analysts typically emphasise the
importance of the overall approach rather than specific rules, seven
steps to good practice in discursive research have been put forward by
Potter and Wiggins (2007) and were used to guide this research
(Appendix H).
The transcripts were initially coded in NVivo, identifying discourses
which emerged from the transcripts when focusing on positioning,
discursive agendas, and the influence of power and context on the
discussion. Key discourses were chosen for in-depth analysis based on
emergence across all four focus groups with reasonable coverage
(summary table in Appendix I). Discourses which occurred across all
groups were chosen to minimise bias. Representative extracts were
selected illustrating the discourses and discursive practices in use
(Jørgensen & Phillips, 2002), ensuring consistency with the analysis of

the transcripts as a whole (Potter & Wetherell, 1987). Extended extracts
are included to allow the reader to judge the coherence and plausibility
of the analysis. Coherence and plausibility form the basis of validity in
DA, alongside grounding analysis in previous research (Wetherell,
2001).
Quality Checks
DA acknowledges that research is itself a discursive activity and
the context of the research and the researcher cannot be partialled out
from the analysis (Jørgensen & Phillips, 2002). Coherence and
plausibility form the basis of validity in DA, alongside grounding analysis
in previous research (Wetherell, 2001). Coherence requires that analytic
claims form a coherent discourse, with all aspects of the analysis being
consistent with the analytic account. Plausibility is in part achieved by
situating the research within existing knowledge, and requires that the
account appears plausible and persuasive (Wood & Kroger, 2000).
Extended extracts have been presented in this write up to allow the
reader to assess both coherence and plausibility in the analysis (Madill,
Jordan, & Shirley, 2000).
Fidelity to DA methodology was ensured by presenting extracts
from the data at a DA researchers’ group and discussing the analysis
and findings with clinical psychology qualitative students. Further the
analysis and findings were reviewed by both my primary supervisor, a
discourse analysist, and secondary supervisor, a clinical psychologist.
Results

Analysis
The key discourses selected for analysis were: balancing medical
and therapeutic discourses, particularly when discussing psychosis and
religious or spiritual beliefs; positioning and the Other, including religion
and spirituality as a proxy for talking about race; and negotiating what
can or cannot be said, principally when sharing personal practice.
Definitions of othering, and medical and therapeutic discourses are
provided in Appendix A.
Balancing medical and therapeutic discourses. The medical
discourse attributes individuals’ religious or spiritual experiences to a
diagnosis of psychosis (Georgaca, 2004). It views symptoms as
indicative of a diagnosable disorder, usually of organic aetiology, and
positions individuals as “ill”. This discourse was present in all groups,
alongside, and in contrast to, a therapeutic discourse, in which religious
or spiritual experiences were viewed as either helpful or unhelpful
(Georgaca & Avdi, 2011). Couching discussions of spirituality or religion
within the medical discourse strongly positions clients as pathological
(Georgaca, 2004).
Extract one. This extract comes from group three, which had eight
members, all third year trainees. It was coded primarily under balancing
medical and therapeutic discourses, but includes disclosure of personal
spiritual beliefs (lines 14-16). The extract is split into two parts for ease
of reading.
Extract 1a

8 C5: mine was with a adult, because she had a psychotic
↑episode and 9 it was all around her, it was all around like
religious ideas and stuff so
10 she’d had experience of kind of erm, something kind of coming
into her
11 and she, something she described as God, and she talked a lot
about
12 like her religious beliefs and this idea that she was like innately
bad
13 and it was like God punishing her in some way, so that was
quite
14 interesting. And quite hard for me, because I don’t believe in
God, 15 (slight laugh) so, I was, I was trying to manage that in
terms of my own 16 (slight laugh) what do I believe about this
kind of thing.
Medical, religious and therapeutic understandings of patient
experience are illustrated in this extract. It forms the response given to
my initial question about people’s experience of discussing religion or
spirituality in clinical work, and focusses on religious, rather than
spiritual beliefs. In starting the discussion, the speaker is responding to
the demands of the focus group setting and my question (Myers, 2007).
She establishes the case as relevant by specifying that the client
attributed the experience to God, which also serves to distance her from
that interpretation (line 11). With this vignette she orients the group to
religion within a medical discourse, with religious experiences attributed
to psychosis (Goffman, 1986; Georgaca, 2004). However, the rising
tone she uses when introducing the term “psychotic episode” (line 8)
and her repeated use of the discourse markers “kind of”, “like”, and “and
stuff”, signal to the group that
she is not overly invested in that description were they to disagree
(Billig, 1988).

The ways in which spiritual experiences are unhelpful to the client
(lines
12-13) are prefixed with “like” and followed with the comment that this is
“quite interesting” (lines 13-14). In describing these things non-factually
(“like”), and as the view of the client, she has taken up a particular
stance (DuBois, 2007), and protected her own position as a non-
judgmental, scientist practitioner (Myers,
2010). The speaker reports discomfort in addressing this topic in
therapy (lines 14-16), and displays unease around disclosing and
questioning her beliefs, which she dispels by laughing (Jefferson, 1984).
Extract 1b
17 R: And how was that
18 C5: Erm… yeah it was ok (2 secs) erm, but I, maybe it was
easier
19 because she was kind of very much, although she was
religious she
20 was very much putting like that experience down to her
psychosis and,
21 and experience of psychotic episode, as opposed to (1.5
secs) actually
22 kind of saying I do actually think kind of God entered me
and all of this
23 stuff. So I suppose I was, it was easier for me to manage it
because I
24 could put it down to a mental health ↑thing as well, because
that’s how
25 she was interpreting it. (1.5 sec) but I don’t know, I can’t
imagine how
26 difficult it would be if you’re saying but I genuinely believed
God, in
27 God, and I believe that God touched me in some way and
other people

28 are just saying “yeah but that’s just your psychosis”, and
like (1.5 secs) 29 I don’t know how that would have played out if
people were doing that 30 differently.
In the second half of the extract, the speaker differentiates the
client’s religiosity from her beliefs with religious content which are
labelled as psychosis. She pauses in line 21, appearing to avoid
contrasting the attribution of experience to psychosis with ‘really
believing it’. The use of the phrases “actually”, “kind of”, and “and all of
this stuff” (lines 21-22) reduce the impact of what is being said. The
client is described as using the medical discourse to make sense of her
experiences (lines 20-21), which the speaker found “easier” to manage
within a mental health setting (Coyle, 2008).
The speaker positions herself alongside the hypothetical ‘believer’
whose
‘genuine’ beliefs are being dismissed as “just psychosis” (lines 25-28),
distancing herself from those making that judgment. This shift from the
medical discourse, which positions the client as psychotic (lines 8-13),
to the therapeutic discourse where one is positioned as alongside the
client, accepting their interpretation of experiences (lines 24-25), meets
the requirement for CPs to respect diverse beliefs (BPS, 2009)
Extract two. The second example of balancing medical and
therapeutic discourses is also drawn from focus group three. The extract
has been split.
Extract 2a

46 C7: yeah, that’s really interesting ‘cause I’ve had similar
experiences 47 about people having protective, erm, things around
errr, their religion.
48 So, erm, when I was working on the inpatient ward actually
49 interestingly it came up more than anywhere else since I’ve
been
50 working. And we had a lady who was very psychotic, and she
had
51 some negative, erm, voices, and she had some positive
voices. The
52 negative voices went away with medication, but the positive
voices
53 didn’t. The positive voice was God telling her she was ok. She
was a
54 nice person, that er, she was valuable and she should be here.
Erm (.)
55 and, interestingly, had a quite interesting conversation with the
56 psychiatrist about why, that meant that then she ↑couldn’t go
home
57 because she still had, these voices. I said those are protective
for her,
58 they (.) they help her function. They are really (.) helping her
still get on
59 with her life. Erm (.) and he was, yeah, he was very [no she
has voices]
60 C1: [s-,s-,s-, so] because it didn’t
61 coincide with his view of reality, that was, erm, blocking her
from 62 returning °back to the community°.
As she introduces this service user the speaker emphasises her
psychosis, stating that she was “very psychotic” (line 50). It seems
important to establish her as a legitimate or even archetypal ‘psychotic
patient’, reinforced by the “negative voices” having resolved with
medication (line 52), aligning with the medical discourse. The distinction
between someone who is very psychotic and someone whose beliefs
are helpful is emphasised. From that point the medical discourse is

attributed to the psychiatrist and religious discourse to the client. The
speaker positions herself outside the medical discourse, arguing against
the psychiatrist, drawing on a therapeutic discourse (Georgaca & Avdi,
2011), emphasising the helpfulness or unhelpfulness of the voices (lines
57-59).
C1’s interjection amplifies the argument against the position
attributed to the psychiatrist (lines 60-62). Her phrasing suggests that
the psychiatrist’s view of reality is no more valid than the client’s,
unusual given the power differential between physician and patient
(Pilnick & Dingwall, 2011). This permits the possibility of alternative
truths, again aligning with the therapeutic discourse rather than the
medical. However, the drop in volume of her voice as she finished
speaking may be a recognition of psychiatry’s continuing power within
mental health services (Georgaca, 2004).
Extract 2b
63 C7: yeh (.) And then, an-, and so that kind of started off a
conversation 64 (1.5 secs) erm, between me and some of the
other patients as well
65 about, religion and religion in terms of erm, mental health, and
just that
66 kind of thing of (.) erm (.) I don’t know people might disagree
with me,
67 but if people say “I am the son of god” or “I am”, erm, you know
“god
68 speaks through me” or whatever (.) instantly in our line of work,
they’re
69 psychotic, there’s something really wrong with them, they’re
grandiose,
70 they’re psychotic. (2 secs) but actually I wonder whether,
sometimes,

71 you know, if it were, if it was a different circumstance and it
was a
72 religious group where people were ↑°speaking in tongues or
73 ↑whatever° [(2 secs), quiet mm’s of agreement] would you see
it as
74 ↑psychotic °experience, I don’t know°. It’s just interesting in
how it can 75 be protective in some (.) situations and not
protective in others.
C7 qualifies the strength of her statement about the assumptions
made in mental health settings (line 66), perhaps pre-empting
disagreement and signalling she does not have an axe to grind
(Edwards, 2003). Most members of the focus group are working in
mental health, and an outright challenge of the medical discourse
dominant in this setting (Bassett & Baker, 2015) may result in counter-
argument. However, despite this qualification, she identifies with clinical
psychology (“in our line of work”, line 68) to support her claim that
individuals reporting religious experiences are positioned as
“grandiose”, ill and “psychotic” (lines 69-70). Her discussion of religious
settings (lines 72-75) is more hesitant, with rising intonation and softly
spoken phrases. It seems that C7 is less confident to speak to these
settings, possibly as some group members are religiously committed.
In this extract and in other groups the term ‘protective’ (Rutter,
1985) was used of religious beliefs as part of the therapeutic discourse
(lines 47,57,75).
This allowed the impact of the belief on individuals’ mental wellbeing to
be assessed, without the need to address their truth or whether TCPs

agree. This is one way that CPs have engaged with spirituality in clinical
settings (Arshad, 2007; Crossley & Salter, 2005).
Positioning and the Other. Although race was not directly asked
about, in all groups it was suggested that discussing spirituality is rare
because of ethnic homogeneity in the South West. Mulla (2012)
highlighted that CPs in her study located spirituality in the otherness of
patients. Othering has been defined as “a process (...) through which
identities are set up in an unequal relationship”
(Crang, 1998, p.61). Constructing the other is a discursive means to
constructing the self and maintaining position and power (Lin & Kubota,
2011; Johnson et al., 2004; Kitzinger & Wilkinson, 1996). By defining the
Other as
“them”, different from ourselves, a self-identity can be established for
“us” which positions us favourably. Othering often occurs on the basis of
race or culture (Johnson et al., 2004; Lin & Kubota, 2011). There are
examples of othering in extracts one and two, as speakers distance
themselves from the client’s position (extract one line 11; extract two
lines 47-50). Within psychology othering of clients, particularly those
with psychosis, can be achieved by positioning them as ill or irrational
(Boyle, 1996).
Extract three. This extract comes from group two, which had four
members, all third year trainees. It follows a question from me about
training, and a joke from B4.

464 B2: It wou-, I, I personally would have found it really helpful to
know
465 more about religion and spirituality because, I, I’m gonna say I
am very
466 ignorant, erm, ok our demographics down here don’t have
huge variety
467 of religions, but elsewhere in the country we would encounter a
lot
468 more [difference] so it would be really interesting to have a bit
of 469 teaching around that to know, you know.
470 B4:[exactly]
471 B2: Some very basics of what you can and cannot say in
certain
472 situations. I dunno, I [think it would’ve been really helpful]
473 B4: [I wonder if part of it] is a sort of south west trap maybe,
that the
474 course has fallen into that trap a little bit it’s just th-, that the
475 demographic’s taken as yeah, white (.) and rural
B2 describes herself as “very ignorant” of spiritual and religious
topics (lines 464-465), and emphases a desire for more teaching in this
area, which would be really helpful (line 464) and really interesting (line
468). Despite initially referencing both spirituality and religion, in line
with previous research (Begum, 2012) she goes on to talk only about
religion, apparently meaning religions beside indigenous Christianity
(lines 466-469). Perhaps to forestall argument, she prefixes her
statement with the disclaimer “personally” (line 464), acknowledging that
the desire for more training may not be shared. Her suggestion that it
would be good to cover “the very basics” (line 471) positions
her as an interested student whose needs have not been met.

The purpose of further training is to know “what you can and
cannot say” (line 471), apparently linked to a wish not to offend people
of diverse ethnicities or religious beliefs. B4 agrees, suggesting that the
course has made assumptions that the local area is “white and rural”
(line 475), implying that spirituality and religion are not relevant, or at
least not problematic, in white, rural areas.
The location of spirituality and religion within the Other has been
noted in previous research (Mulla, 2012). All focus group members were
white. By constructing a discourse of these topics as relevant elsewhere
in the country (lines 466-468), rather than the white South West (line
475), the speakers distance themselves from spirituality or religion as
personally relevant. This may avoid the uncomfortable thoughts about
personal beliefs reported in extract one, and establish individuals as
speaking from a more objective, external position. In focus group one an
individual highlighted the othering process she felt was occurring in the
group.
136 A6: I think in my experience it’s been almost a bit othering, I
think if it
137 was sort of a predominant sort of Christian religion it won’t
necessarily
138 be attended to, but I think if there’s someone from a different
ethnic
139 background or something that some people start thinking about
religion
…
156 A6: I, it, it’s felt to me sometimes like services, when they’re
looking at
157 people, perhaps from a different ethnic background or
something it’s

158 like, it, they’re somehow different therefore be different,
therefore in 159 that sort of respect rather than the kind of
religion being central to their 160 presentation or their
difficulties.
This extract reinforces that religion is only considered relevant
when nonindigenous, other and unknown. This is linked by A6 to
ethnicity (lines 138,157), and therefore race (van Dijk, 1996), being
restated with the qualification that it was how things had felt to her (line
156), dispelling argument. Othering often occurs on the basis of race
(Johnson et al., 2004), preserving the status quo and silencing the
Other (Kitzinger & Wilkinson, 1996). As noted in previous research
(Arshad, 2007; Mulla, 2012), religion appears to be aligned with race,
sometimes under the broader heading of culture.
Extract four. The following extract is from group four, which
had four qualified CP members. It follows me asking about
spirituality and religion in training.
495 D3: And I mean I remember pre-training I worked up in the
West
496 Midlands and it was rea-, obviously very multi-cultural. And we
had, we 497 had training on, on all the different religions and
spirituality etc. 498 Because of the, um, the great possibility of
putting our, a big foot in 499 (laughing) putting our foot in it.
500 Mmm
501 D3: um, and that, but that was very useful but, down in
Somerset it,
502 (laughing) I haven’t had much use for a lot of that. Um (.)
503 D4: it’s changing a little bit [(.) occasionally, I had] a, a very
spiritual… 504 Burmese, lovely lady, who used to=

505 D3: [a little, you see a little]
506 D4: =Salom’ed me when she came in. She was, you just have
to
507 take it in your stride. [mm] and get her up off the floor and sit
her in a 508 chair (.) And she was absolutely charming
This extract is an example of race and spirituality being combined
under the heading “culture”. The more culturally diverse West Midlands
is assumed to be somewhere that ideas of spirituality and religion are
more relevant. Having positioned herself as someone who knows about
diversity of spiritual and religious beliefs because of previous work (lines
495-497), D3 paints Somerset as somewhere that her existing religious
and racial knowledge and sensitivity is not required (lines 501-502). She
laughs when discussing the possibility of
‘putting one’s foot in it’ when working with individuals from another race
or religion (lines 498-499), apparently expressing discomfort at the
thought (Jefferson, 1984). This may be due to how negative it is to be
seen as prejudiced or racist, particularly at work (Potter & Wetherell,
1988).
As race is a taboo topic (Augoustinos & Every, 2007), the link
made between religion, spirituality and race may make these topics
even more difficult to discuss. By situating spiritual concerns as things
that happen “elsewhere” in the country, in the Other of a different ethnic
group, it perhaps becomes easier for group members to discuss them,
as they position themselves as external and objective. The overall
message from D3 in this extract appears to be that although it may be
regrettable that these topics are not discussed, it is a product of

geography and demographics, rather than clinician choice (lines 501-
502).
The lack of spiritual or religious material in Somerset is challenged
by D4
(line 503), and D3 acquiesces, acknowledging that there is ‘a little’ (line
505). D4 then talks about a past client, presenting her nationality and
spirituality together, furthering the alliance of spirituality and religion with
ethnicity (lines
503-504). She speaks highly positively of the “lovely” lady, who was
“absolutely charming” (lines 504,508), but discusses her spiritual
behaviour as an idiosyncrasy to be “taken in your stride” (line 507). The
matter appears not to be taken seriously, as you need to “get her up off
the floor and sit her in a chair” (lines 507-508), implying that then the
real work can continue.
Extract five. The next, brief, extract comes from focus group
three, comprised of eight third year trainees. The group had been asked
which patient groups they would be more or less likely to discuss
spirituality or religion with. They suggested that spirituality and religion
were less relevant in CAMHS, as young people are “less religiously
orientated”. The below exchange followed.
563 C1: what about young people that are being radicalised?
564 (4 secs)
565 C2: not in North Devon
566 Group: (laughter/giggles)
567 C3: only with this surfing cult.

568 Group: (deeper laughter)
C1 challenges the discourse that was in place in the
discussion, namely that these topics were not relevant for CAMHS
settings. Although explicit mention is not made of race, the
introduction of the racially loaded term “radicalisation” produces a
long pause (line 564), before its relevance is denied and discomfort
diffused by laughter (lines 565-568).
Radicalisation is an increasingly common phrase, including within
the NHS (e.g. prevent training; NHS England, n.d., para. 4), and is,
like terrorism (Jenkins, 1980), a power-loaded term. While
radicalisation is not defined in terms of religion or race, Muslim
individuals form the majority of referrals to the UK’s Channel
programme, which aims to support and divert those at risk of
radicalisation (National Police Chief’s Council, n.d., para.1).
The discomfort both of the challenge and the introduction of a
political and racial term is managed in this extract by denial and
humour (Jefferson, 1984). Jokes are made and the laughter of the
group intensifies, in line with how race is often managed in popular
culture (Howells, 2006). I reoriented the group to think about why
spirituality and religion did not feel appropriate to discuss in
CAMHS, but the idea of radicalisation was not returned to, possibly
as that discourse had been effectively avoided within this
exchange.

Negotiating What Can Be Said. Across the groups some
participants shared their personal religious or spiritual views and
practices. As prior research has reported CPs’ and TCPs’ reluctance to
disclose their position to colleagues or to clients (Baker & Wang, 2004;
Betteridge, 2012; Malins, 2011; Mills, 2010), how this topic is negotiated
within professional groups is key for facilitating meaningful discussion.
Extract six. This extract is from focus group one, carried out with
nine second year trainees, with whom I had minimal previous contact.
This extract occurred close to the end of the hour long group. The
extract is split into two parts.
Extract 6a
722 A4: I wonder if people are less willing to invest time into it because it’s
not 723 spoken about that much in this day and age and thinking about
extremist
724 views like Richard Dawkins that religion’s going to die out, it
won’t exist one
725 day so is that just us like (inaudible) it as well
726 R: he goes further than that, he says it’s um, damaging doesn’t
he= 727 A4: =yeah, he does yeah.
728 A1: But then if you flip it round you’re like is science not just another
form of 729 religion that people have blind faith that you can find the truth.
730 (inaudible) (Group laughter)
731 A2: it’s really interesting having this conversation actually in a
clinical
732 setting compared to when I was working in research where I
was pretty
733 much the only person who practiced a religious (.) faith. And
that was

734 seen as like this major, flaw (laughs) [in my ability to think
clearly or
735 something] ((blushed))
736 (Group laughter)
A4 has previously disclosed his position as an atheist within the
focus group, which received no comment. Here he begins to expand on
that position with reference to a prominent atheistic scientist. While
drawing on his theories, A6 distances himself from Dawkins’ views,
calling him ‘extremist’ (line 723).
When I introduce the more controversial of Dawkins’ arguments, that religion is
harmful (line 726), this discourse is rejected by the group, with a hitherto
unmentioned discourse of science as a version of religion presented (lines
728729). The group laughs, signalling their solidarity and togetherness
(Adelswärd, 1989). A1 equates scientific and religious views of reality (lines
728-729), permitting alternative truths as part of the therapeutic discourse (as
in extract one). A2 then discloses her own religious faith (line 733). She appears
embarrassed (blushing, line 735) and laughs, in contrast to stating that previous
colleagues viewed her as flawed and irrational (line 734). The group join with
her laughter, perhaps working to mitigate her embarrassment (Adelswärd,
1989). A2 had not directly addressed her beliefs previously in the group; her
cohort might have known of her beliefs, but I did not.
A2’s statement that past colleagues considered her thinking to be
compromised because of her religion, and dismissal of this view with the
phrase
“or something” (line 735), may have functioned to forestall similar
argument from the group (Billig, 1988). This discourse of religious belief

as indicating irrationality is similar to the medical discourse of psychosis
mentioned above (Boyle, 1996). The distinction she draws between her
previous academic setting and the current clinical context (lines 731-
732) highlights that different discourses may be at work, and makes
positioning her as irrational less accessible from the current clinical
frame. There is similarity between the academic and medical discourses
on the one hand, and clinical, therapeutic discourses on the other.
Extract 6b
737 A6: That’s crazy
738 A2: tha-that’s the science that informs our practice of course
739 A6: Yeah (.) yeah that’s true, it’s interesting to think actually. I
think we
740 can quite often overlook it as a resource as well because
there’s so
741 much there with the religious communities that’s really positive
and you
742 know we go to the third sector organisations like charities and
you
743 know all sorts of things but I think we’re I dunno maybe I’m
over
744 generalising but we’re maybe more reluctant to kind of get
involved,
745 you know if someone does hold a religion, then getting
involved with
746 their network [their] religious network, whatever that might be=
747 A1: [yeah] =And absolutely
actually
748 because my cousin, um struggles with um bipolar and her like
my
749 cousin and family are all, um Mormon, and actually the support
they
750 received from the community is massive, erm, like not even j-,
like
751 financially as well because if you think about a lot of churches
people

752 pay in money to support the community and stuff and like
financial
753 when she couldn’t work, she’d been admitted and all that stuff
like, it-I,
754 you are right actually, there’s a lot of stuff we could tap into
there=
755 A6: =The really like practical aspects of religion
Following A2’s disclosure A6’s response is supportive, calling the
attitudes of past academic colleagues “crazy” (line 737). She appears
keen not to alienate other members of the group, adding “I dunno
maybe I’m over generalising” (lines 743-744) before speaking from a
position within psychology, of a professional reluctance to engage with
religious groups (lines 744-746). She simultaneously distances herself
from religious individuals (lines 745-746), making reference to religious
communities, a phrase which can be shorthand for minority ethnic
groups (Bauman, 1996).
A6 describes religion as a possible resource which psychology
could tap into (line 740-724). A1 agrees with her (line 747) and recounts
personal experience of religion being socially and financially helpful
(lines 748-754). An explicit move is made away from the difficult topics
of personal belief and professional disagreements. A1 differentiates
“just” social or spiritual support from financial support (lines 751-753),
which is furthered by a latched statement from A6 highlighting the
“practical aspects” of religion (line 755). These more concrete and
positive ideas seem easier for the group to discuss than the more
controversial topics of what individuals do or do not believe.

Discussion
This study aimed to explore what discourses TCPs and CPs from
South West England used to manage discussions of spirituality and
religion in clinical practice. The key discourses identified demonstrate
how Othering (Johnson et al., 2004), particularly in terms of race (Lin &
Kubota, 2011), can be used to position spirituality as something distant,
allowing discussions to appear more objective and not relevant to work
in the South West (extract four). The medical discourse of spiritual and
religious experiences as indicative of psychosis (Georgaca, 2004) was
also drawn on. TCPs could thereby partially avoid engaging with their
own beliefs (extract one), but experienced tension with the therapeutic
discourse (extract two). The analysis illustrated how medical and
therapeutic discourses were used in turn to allow TCPs and CPs to
occupy positions both as distant from religious experiences, and yet
distant from the medical discourse which might be seen to pathologise
them.
An apparent distinction exists between acceptable personal beliefs
and what can be expressed in professional settings (extract six). This is
not unique to psychology, with the UK media reporting cases where
personal beliefs and professional practice have been differentiated,
including bakers refusing an order due to religious beliefs (BBC, 2016),
and a potential headscarf ban in some workplaces (BBC, 2017). This
analysis demonstrated how groups of clinical psychologists can reject or
take up different discourses in order to manage the demands of a focus

group (Myers, 2007) whilst also moderating the views expressed or
permitted within the group.
The analysis shows some discursive strategies TCPs and CPs use
when discussing spirituality in focus group settings, which are common
to other taboo topics. These include laughter (Jefferson, 1984), tentative
or personalised speech (Edwards, 2003) and discourse markers such
as “you know” or “like” (Edwards, 2003). Although spirituality and
religion were asked about, most of the talk focused on religion, despite
a preference being stated for “spirituality”. This is similar to past
research (Begum, 2012; Harbidge, 2015), and may be linked to poor
familiarity with appropriate language (Crossley & Salter, 2005) or the
inadequacy of language to capture spiritual ideas (Coyle, 2008).
Analysis of the discourses in use expanded previous findings by
highlighting that not only was religion discussed more frequently than
spirituality, particularly when discussing examples from clinical
experience, it was often, though not exclusively, connected with othering
on the basis of race, culture or ethnicity.
The extracts and analysis provide insights into how spirituality and
religion are discussed and negotiated within groups of TCPs and CPs.
Although limited to a relatively small number of clinicians in South West
England, some possible implications for training and practice can be
cautiously drawn out.

Implications for Clinical Psychology Practice
Psychology’s dual position as an academic discipline and clinical
profession creates tension for TCPs. Spirituality appears to be more
acceptable in clinical or therapeutic contexts than in medical or
academic ones, and TCPs are explicitly positioned between the two.
The medical discourse linking spirituality with psychosis (Georgaca,
2004) must be reconciled with the requirement for culturally sensitive
formulation (BPS, 2014), recognition of vital nonspecific relational
factors such as validation (BPS, 2014), and the ethical value of respect
(BPS, 2009). This tension was highlighted in extracts one and two,
arising across all groups. Making the contrast explicit in training may
allow more dialogue and reflection about how different professional
identities can be accommodated.
Race is a key area of diversity and has been poorly differentiated from
religion by CPs in some past research (Arshad, 2007; Mulla, 2012). In
this study
TCPs and CPs across all groups linked religion and race, and viewed
the South
West’s ethnic homogeneity as explaining the lack of engagement with
spirituality and religion in their practice. Facilitating discussion of
othering in training, for example when discussing social identity theory
(Tajfel, 1981), may be helpful for TCPs, and could highlight the potential
for religion and spirituality to function as shorthand for many kinds of
othering. Clinical vignettes could promote discussion of how religion or
spirituality may present, serving to reduce the stereotype that it occurs

primarily with clients from minority ethnic groups or diagnosed with
psychosis. This may help to counter the position taken up within the
focus groups of participants as interested (extract three) or informed
(extract four) clinicians, who do not discuss spirituality due to its
irrelevance to local populations.
Clinicians may avoid addressing these topics if they view the risk
of offending clients as more damaging than the omission of spirituality.
However, it is possible to equip non-religious professionals to interact
helpfully around religion with individuals for whom it is important (Good,
2010; Worthington &
Sandage, 2001). Facilitating discussion of spirituality during training
may equip TCPs to talk more helpfully and comfortably with clients
when qualified. For example, experience of taking a spiritual history
from patients while training improves clinicians’ view of, and comfort in,
doing so (Gonçalves et al., 2016). If discussing spiritual or religious
matters was included as a competency in training, this may increase
exposure and help to decrease difficulty in these areas.
NHS Education for Scotland (2009) recommends that spiritual
education for health professionals incorporates time to discuss personal
and professional experiences of spirituality. However, psychologists who
value religious beliefs or spiritual experiences may fear being positioned
as irrational (Boyle, 1996) if they share their position. In this study
participants used rhetorical strategies to avoid offending others, and
positioning and stance-taking to preserve their sense of identity whilst

expressing potentially controversial views. The inclusion of facilitated
debates in training which require individuals to adopt a more extreme
stance, could give permission for controversial ideas to be expressed
and considered without threatening trainees’ identity as “good” TCPs.
The idea of religion as a potential protective factor or resource
(extracts two and six) may help scientist-practitioner TCPs and CPs to
engage meaningfully with spirituality (Thayne, 1998). Focussing on the
potential benefits (or risks) of spirituality could make discussion of how
to integrate this into practice more manageable, as the truth of beliefs
and personal positions can be avoided.
Limitations
This study relied on individuals volunteering to participate, which
may have resulted in a bias towards those with strong views about
spiritual and religious topics. Specifically highlighting the value of
hearing from disinterested parties aimed to reduce this, and positively
the majority of potential participants did volunteer.
The study was skewed towards the views of current trainees (three
of four groups). Two qualified groups were planned, but the second was
cancelled by the host Trust due to budget constraints. As the context of
clinical psychology training is one of assessment and performance, with
individuals regularly observed and evaluated, there is a need to be seen
to “get it right” and respond with acceptable clinical psychology
discourses. Although this research aimed to examine the normative
discourses which focus groups generally (re)produce (Smithson, 2000),

this also limits what will have been shared. This is likely to have been
particularly pronounced in trainee groups where participants knew each
other well and professional norms were developing (Leask, Hawe, &
Chapman, 2001). The participants who are part of my training cohort
know that I have personal religious beliefs, and other participants may
have assumed my motivation for this research. This will have influenced
what was said, as individuals maybe tried not to offend, to educate, or
challenged assumed views.
Demographic information, including religious and/or religious
beliefs, was not collected for TCPs and CPs taking part in this research.
Whilst this meant that these labels did not influence my interpretation as
a researcher, it also means that impact of beliefs cannot be
systematically explored, nor individuals self-identified ethnicities
examined.
All participants live and work in South West England. As noted in
the groups, the area is ethnically homogenous, and a lack of exposure
to cultural and religious diversity was reported. It is possible that this
lack of exposure means individuals were less comfortable discussing
these topics, and findings may not be generalizable to clinicians working
elsewhere. Furthermore, that the majority of the participants (both CPs
and TCPs) had an existing relationship with myself will have impacted
how the focus group was facilitated, what participants felt able to share,
and, to an extent, the analysis. There may also have been concerns

from TCPs taking part about the limits of confidentiality for research
being undertaken in the department where they were also training.
Researcher Reflexivity
In qualitative research on spirituality (West, 2009) the relationship
of the researcher to the material needs to be made clear via personal
reflexivity (Madill et al., 2000), which acknowledges how personal
interests and values influence research from initial ideas to outcome
(Banister, Burman, Parker, Taylor, & Tindall, 1994). Functional reflexivity
is key in DA and requires
“continuous, critical examination of the practice/process of research to
reveal its assumptions, values and biases” (Wilkinson, 1988, p.495).
My own position as a committed Christian and TCP influenced my
interest and opinions on spirituality and religion, and the saliency of
discourses during analysis. My clinical experience of individuals of faith
expressing fear of judgment or criticism for their beliefs also influenced
my choices and interpretations. As a member of the clinical psychology
profession, and of the same training cohort as two of the groups, there
may have been aspects of culture or professional discourses which I
overlooked. This was mitigated by receiving feedback from discursive
researchers outside the profession. Such
‘confessions’ do not bracket the influence of these factors (West, 2009),
and should not reduce criticism of observed stake and interest (Potter,
Edwards, & Wetherell, 1993), but hopefully can help readers to critically
assess their impact on this research.

The assumptions of DA about the function and use of language
have been outlined above. My choice to focus on positioning, rhetorical
strategies and identity influenced the discourses identified from the
transcripts. With more time and resources further analysis would be
possible and other discourses could be
identified.
Further research with professional cohorts working in areas which
are more ethnically diverse would help to establish whether positioning
religion as Other occurs generally on the basis of race, or if this is
heightened by a lack of exposure in clinical practice. Similarly, repeating
this research with cohorts which are more ethnically diverse would also
be useful. Conducting DA on course materials which address spirituality
could also help to examine the ways that training may influence and
perpetuate professional discourses in this area.
Conclusion
This study adds to previous research into the professional attitudes
of psychologists to spirituality and religion by examining the normative
discourses that were constructed between professional cohorts during
focus group discussions. Three key discourses were identified, giving
insight into how professional cohorts of TCPs and CPs manage
discussion of these difficult topics. These were: balancing medical and
therapeutic discourses, particularly when discussing psychosis and
religious or spiritual beliefs; positioning and the Other, including religion

and spirituality as a proxy for talking about race; and negotiating what
can or cannot be said, principally when sharing personal practice.
Ensuring that clinical psychologists have an awareness of the
different discourses in use within the profession and how these may
impact clinical practice is important. Explicit discussion of the medical
and therapeutic discourses likely to arise across different settings
should be encouraged, including how these can constrain discussions
around difficult topics. Training should equip psychologists to have an
awareness of othering, particularly in relation to religion or spirituality
and race, and the potential effects this could have on power and
engagement in therapy and broader work. The discursive practices
highlighted here, and implications for training, have relevance not only
to spirituality and religion, but also to other “difficult” topics, including
sexuality,
ethnicity and race.


