


College Students’ Experiences and Perceptions of
Mental Health in a Campus Culture
Chapter 1: Introduction to the Study
College is traditionally a time of transition as individuals leave home (National
Alliance on Mental Illness, 2021). College students learn foundational approaches to
taking care of their health. Further, mental illness impacts a significant number of
college-age students (ACHA, 2019). The onset of mental illness comes before the age of
24, and a significant percentage of individuals this age attend college (Kuhlman et al.,
2019). The American College Health Association (ACHA, 2019) found that 24% of
students reported having been diagnosed or treated for anxiety and 20% for depression.
These numbers are likely a low estimate because students who are not diagnosed or
treated for anxiety or depression may also have intermittent symptoms of mental illness.
Better understanding of students’ attitudes, behaviors, and beliefs surrounding their
mental health may help determine interventions to transition the culture to a mentally
supportive one. Academically, postsecondary students’ success can rely on the level of
student wellness, both mentally and physically (Condra et al., 2015).
The current qualitative study addressed mental health from the perspectives of
college students and their beliefs surrounding their behavior regarding communicating
about mental health, including actions when having mental health issues, the campus
norms, and how these norms impacted the campus culture. Qualitative interviews and
artifact collection with college students helped me explore how the college culture

impacted communication surrounding mental health. Understanding underlying cultural
implications surrounding mental health can be used to improve overall health by creating
an environment and culture of health (both mental and physical), which can impact
academic achievements (ACHA, 2019; Baik et al., 2019; Capone et al., 2020; Chang et
al, 2020; J. I. Chen et al., 2016; Condra et al., 2015; Corona et al., 2017; Downs &
Eisenberg, 2012; Gardner & Kerridge, 2019; Holt et al., 2019; Lambert et al., 2019;
Roming & Howard, 2019; Roy, 2018; H. Shea et al, 2019; Wada et al., 2019; Wieland &
Kucirka, 2020).
Chapter 1 provides the justification for this study and addresses the gap in the
literature. This chapter includes the background of mental health on college campuses and
young adults, the problems related to the culture and communication surrounding mental
health that were addressed, and the purpose of the study. The chapter also covers the
research questions, theoretical foundation, nature of the study, definitions, assumptions,
scope, and limitations. The chapter concludes with the significance and social change
aspects of the study.
Background
Health is a complex, multidimensional phenomenon that can be impacted by the
body and mind of a person was born and by environmental factors and their social
environment (World Health Organization [WHO], 2020). Mental health is one important
facet of the health of an individual (Centers for Disease Control and Prevention [CDC],
2021). The mental health continuum models focus on the spectrum of mental health and
where humans may fall at any given time (S.-P. Chen et al., 2020; Keyes, 2007).

Mental health is a significant issue, and suicide is the second leading cause of
death for people age 15–34 in the United States (CDC, 2021). Mental health issues such
as depression and anxiety have increased in children age 3–17 (CDC, 2021). Mental
health issues are continuing to increase in children from birth to age 17, which can
indicate future increases in mental health issues in higher education students
(LebrunHarris et al., 2022). This can lead to a larger number of college students starting
out with existing mental health issues and/or developing them as they begin a new life
phase. Mental health issues are increasing and impacting the population worldwide, and
mental health issues continue to increase in college students (ACHA, 2019; Healthy
Minds
Network, 2023; University of Minnesota, 2021).
Many studies indicated causes for mental health issues. For example, underlying
cultural issues contribute to feelings of otherness that can impact mental health of ethnic
or racial minority students (Cokley et al., 2017). Assimilation into the college community
can cause a cultural stressor, while at the same time the Latina/o cultural value of
community and family can help maintain a health mental state (Corona et al., 2017;
Hernández & Villodas, 2020). The feeling of differentness regardless of race or culture
can also lead to the stigma effect related to mental health that causes people to avoid
addressing any mental illness issues (Peter et al., 2021). Studies have found that college
students are unlikely to seek help such as counseling, and this can be related to beliefs
that counseling is ineffective (Downs & Eisenberg, 2012; Kuhlman et al., 2019).

Unspoken campus cultural rules can determine how comfortable students are
communicating their mental health issues with each other, faculty, and staff. Student
well-being can be improved through the environment, culture, and communication or the
overall setting in which students are learning and living (Baik et al., 2019). When
students reported more communication regarding mental health issues, personal stigmas
regarding mental health decreased (Carmack et al., 2018). Supporting effective
communication and mental health storytelling can encourage sympathy and resulting
social support (Y.-I. Lee et al., 2019). Issues with accessing mental health counseling
when needed and the stigma associated with mental illness are also associated with
sociocultural barriers (Topkaya et al., 2017). Improving the mental health culture and the
resulting communication around mental health could increase the number of university
students who reach graduation (Baik et al., 2019). Understanding the underlying cultural
factors directly from students may reveal possible interventions that can improve mental
health, thereby improving the future for students once they graduate.
The WHO (2019) accelerated its work with creating universal health coverage for
mental health in targeted countries. WHO sustainable development goals include
decreasing suicides and many other goals related to mental health. Although there has
been much research about mental health and young adults, mental health issues continue
to exist and are often found to be increasing (ACHA, 2019; Healthy Minds Network,
2023; University of Minnesota, 2021). The onset of diagnosed mental illness most often
occurs before the age of 24, an age when many are traditional college students are
enrolled (Kuhlman et al., 2019). Understanding students’ needs, communication, and

relationship to the culture may provide insight into interventions that could reverse this
trend (Giamos et al., 2017). Understanding the cultural impacts can allow for changes that
encourage students to seek help, which may improve overall campus mental health (J. I.
Chen et al., 2016). Highlighting ways to improve overall health trajectories at the crucial
stage when young adults are learning how to live and work independently may positively
impact individuals and society.
Problem Statement
This project focused on campus mental health and students’ experiences with
anxiety and depression on the college campus. The social problem addressed in this study
was that mental health issues in college students are increasing, and a better
understanding of the issues may lead to more effective solutions. In the fall of 2021
survey by the ACHA, 50.8% of students had a moderate psychological distress score, and
22% had a serious psychological distress score. The Healthy Minds Network (2023)
found that 22% of students had major depression, 41% had depression, and 34% had
anxiety. At the college where the current study took place, 20.8% of students reported
being diagnosed with anxiety, and 15% reported being diagnosed with depression within
the past 12 months. Furthermore, almost half of respondents (47.5%) reported having
been diagnosed with anxiety within their lifetime, and 42.5% reported being diagnosed
with depression within their lifetime. Data at the regional and state level also showed
significant mental health issues statewide, especially in the northeastern region (Kjos et
al., 2020). Statewide, data showed that 28.7% of individuals reported symptoms of
depression and/or anxiety (CDC, 2017). Increasing rates of depression and anxiety are not

uncommon in higher education (ACHA, 2019; Healthy Minds Network, 2023; University
of Minnesota, 2021).
Campus culture is an amalgamation of faculty and staff culture along with
undergraduate and graduate student culture. There are many different social groups and
cultural elements within these groups. Additionally, the focus on achievement and ability
can lead to neglected individual well-being and associated problems with mental health
(Lambert et al., 2019; Wada et al., 2019). A college campus has a fairly closed
community, as many students live, work, and go to school on the campus. The culture of
a community at the basic level is defined as how people perform activities and how they
interact with each other (Henderson et al., 2018). Mental health culture is defined by how
students address their mental health issues and how mental health issues impact fellow
students. For example, students’ perceptions of mental health norms and existence of
negative stigmas impact their willingness to seek help (Henderson et al., 2018), which
can exacerbate issues. There is a stigma associated with mental health, and a transformed
campus culture has the potential to impact that stigma and promote increased openness
surrounding mental health issues (Link & Phelan, 2006).
Some research has been done on the campus culture relationship and how
elements of the culture, such as communication, impact health, but more research needs
to be done to determine how to change the culture to improve students’ mental health
status (J. I. Chen et al., 2016; De Somma et al., 2017). The gap in research was the lack of
information about how to change campus mental health culture. The research also had

been quantitatively focused. The current qualitative study provided a more in-depth look
at the individual level, providing insight on positive social change opportunities.
Purpose of the Study
The purpose of this generic qualitative study was to explore mental health culture
at a college setting for first-year students by exploring communication methods used by
students. The culture of a community and how individuals communicate with each other
can have a fundamental impact on the health of that community, and a better
understanding of the culture may lead to more effective interventions. The study involved
a social constructivist and constructionist approach and included semistructured
interviews and artifact collection to obtain data regarding student views on the mental
health culture at the college. Increasing understanding of mental health culture may allow
for more focused interventions and changes at the college to increase students’ overall
well-being. The current study supported the overall purpose of an educational setting to
provide a community that supports learning and enriches human life.
Research Questions
The primary research question was the following: What are the cultural norms in
regard to mental health in the individual and communication of mental health issues? The
secondary research questions were as follows:
•What were students’ perceptions and experiences of anxiety in themselves and
others at the college campus?
•What was their relationship with anxiety and student learning?

•What were students’ perceptions and experiences of depression in themselves
and others on the college campus?
•How did the campus culture support or hinder mental health?
•What were potential solutions for improving and maintaining student
wellbeing on campus?
Theoretical Framework
The theory of planned behavior (TPB, Ajzen, 2021) was used to explore behaviors
and beliefs related to the mental health culture on a college campus. The TPB can be used
to understand how individuals’ beliefs and attitudes impact student intentions surrounding
mental health and responding behavior (Ajzen, 2021). Two perspectives that were
considered for my research were the social science perspective, which addresses how
people interact with one another, and psychological perspective, which looks at why
people behave how they do. The conceptual framework related to social constructionism
and constructivism was also used to explore existing perceptions. Increasing
understanding of how perceptions and behavior are connected related to mental health
may lead to positive change (J. I. Chen et al., 2016).
The TPB is useful to predict the connection between behavior and people’s
attitudes (Edberg, 2015) and has been used to study mental health culture on a college
campus. For example, J. I. Chen et al. (2016) found that campus culture can be an
important tool to consider when working to improve mental health. Another perspective
was the feeling of belonging on a college campus and how that influences students’
mental health (Downs & Eisenberg, 2012). In addition, the social network theory and

social support theory have been used to examine individuals and how connected they are
within their community (Fertman & Allensworth, 2017). These connected feelings denote
a sense of belonging that impacts social health. When community bonds are strong, with
strong social ties, interventions can often be more impactful (Fertman & Allensworth,
2017). I conducted one-on-one semistructured interviews with first-year college students
to create a better understanding on their thoughts and beliefs related to mental health.
Nature of the Study
I took a social constructionist and constructivist qualitative approach and used
semistructured interviews and artifact collection with first-year traditional college
students to collect data that would aid in understanding the mental health culture on the
campus. Social constructionism and constructivism are used to determine an individual’s
reality, how they communicate, and the relationship to the community culture of mental
health (Patton, 2014). Current participants were asked to provide artifacts related to the
questions before the interviews, such as pictures, items, phrases, and lyrics that related to
their beliefs and perceptions regarding mental health. I collected a total of six artifacts
over the course of the 2 weeks preceding the interviews. The artifacts provided breadth
and depth to participants’ responses and allowed them to think about the questions from a
unique perspective. This allowed for a more complete and detailed question response.
The coding process was used to develop themes that were used to answer the research
questions. Attention was given to qualities and relationships of codes that pertained to
mental health culture (see Saldaña, 2016).

The study focused specifically on a small, private, college in the Midwest United
States. The on-campus traditional student population was a little over 1,500. Although the
total population was a little over 4,000 (including online and graduate students), this
research focused on the traditional, on-campus students. The college conducts a health
survey biennially to assess the health of the students. The data showed a marked increase
in students who reported mental health issues such as depression and anxiety between
2015, 2017, 2019, and 2021.
Definitions
Anxiety: Having excessive worry that can cause symptoms such as fatigue,
difficulty concentrating, or irritability (Weber, 2021).
Culture: A group of people’s customs, thoughts, and behaviors. Groups can be
people living in a similar area or participating in similar activities. Cultures can have
varying homogeneity and are an amalgamation of backgrounds and beliefs. One aspect of
culture is how the customs, thoughts, and behaviors are communicated within the
community:
•The culture of health can take on an individualistic or collective approach. The
overall culture in the United States is generally individualistic, with the rights
and desires of any one person taking precedence over the overall health and
well-being of a community (Kashihara et al., 2019).
•Mental health culture was defined by how students address their mental health
issues and how issues with mental health impacted fellow students. For

example, students’ perceptions of mental health norms and existence of
negative stigmas impact their willingness to seek help (Henderson et al.,
2018).
•Campus culture refers to the unique culture that develops on each college
campus and is often what draws students to a location, along with desired
academic tracks. Campus culture refers to the collective nature of how
students think, act, and behave (J. I. Chen et al., 2016).
•Academic culture impacts mental health when there is an ability-focused
climate compared to a love-of-learning focus (Wada et al., 2019). Students
can be dissuaded from taking care of their mental health because of a fear of
losing academic status.
•Culture of belonging is the feeling that students are part of the community
where they live, work, or participate. Having a sense of belonging within the
community is one of the dimensions of mental health (Keyes, 2007).
Depression: When an individual is feeling sad, irritable, or empty often or over an
extended period of time (WHO, 2020).
Health: The well-being associated with the mental, physical, and social aspects of
an individual (WHO, 2020). Health is not only the absence of a disease or sickness and
can occur along a continuum with varying degrees of health.
Help-seeking behaviors: The resources an individual looks to when dealing with
mental health issues or illness, such friends, counseling services, or medication (either
prescribed or self-medicated; Chang et al., 2020).

Mental health: An aspect of overall health that focuses on the state of a person’s
ability to recognize their abilities, to function effectively and positively with others within
their community, and to live effectively with normal stress (WHO, 2003).
Mental health continuum: A continuum model in which all individuals fall on the
continuum at any given time. Different models have various categories along the
continuum. Keyes (2002) grouped people into languishing, moderate, or flourishing
mental health categories. A model developed by the Canadian Department of National
Defense also had indicators designating where a person would fall at any given time
along the continuum with options for maintaining, improving, or treating mental health
depending on where the person fell at any given time (S.-P. Chen et al., 2020).
Mental illness: When an individual is on the end of the continuum where there is a
defined sickness related to mental health. An individual can have a diagnosis of a mental
health issue (such as anxiety or depression) and not have an illness at any given time
(Keyes, 2007).
Stigma: A negative labeling of anyone with mental illness or mental health issues.
There are two perspectives related to stigma: self-stigma and public or social stigma.
Self-stigma refers to prejudices individuals feel toward their mental health, and public or
social stigma refers to how they view others’ mental health (Kuhlman et al., 2019).
Traditional-age college students: Students generally between the ages of 18 and
22 living on campus and attending school mostly in person, taking part in the community
that exists within this age group at the college.

Traditional student: Students who enroll in college directly after graduating from
high school, live on-campus, and are full-time students (University of Minnesota, 2022).
Assumptions
The research was qualitative and included semistructured interviews and artifact
collection. Assumptions made regarding the qualitative nature of the study were that each
participant brought their own perspectives and honestly conveyed their thoughts. The call
for participants was voluntary, and I assumed that a variety of perspectives would be
obtained. I also assumed that participants would participate freely and honestly without
fears or concerns that their personal information would be shared with others.
The theory used was the TPB, which involves looking at beliefs to predict
behavior intentions. This study addressed cultural impacts of individual perceptions
related to mental health. The TPB constructs include behavioral, normative, and control
beliefs, and I assumed that these constructs need not be equal (see St. Quinton et al.,
2021). The TPB can explain the relationship between behaviors and beliefs regardless of
whether interview participants are accurate in their perceptions. The theory is a continual
work in progress, and research continues to be done exploring its application and validity
(Bosnjak et al., 2020). Mental health and human behavior are complex, and assumptions
will be continually applied, and models continually questioned.
Scope and Delimitations
The scope of this study included exploring experiences related to mental health
and culture in a college community. The focus on culture and communication was to
explore what changes could be made across the community to reduce stigma, increase the

supportive nature of the campus, and improve overall health. The college chosen was a
small, private, Catholic college, and the students who were invited to participate were
first-year traditional students. This population was chosen to gather information on the
perspective of students when they first join the community. The TPB and conceptual
frameworks of constructionism and constructivism were chosen to explore the gaps
between intention and action related to caring for mental health. The study frameworks
were also used to increase understanding of the phenomenon of public and personal
stigma and associated impacts that affect help seeking. Findings may be used for
traditional college students at similar colleges and may provide information for college
students in other settings.
Limitations
One possible issue that was addressed was any potential relationship with students
and interviewing them about mental health. Because the study was on students where I
had taught, I did not interview students whom I had current or previous academic
relationships with (see Walden University, n.d.). Consent forms were also clear and
avoided any teacher–student conflicts.
Another issue is whether the research being conducted would be valid and
relevant (see Rudestam & Newton, 2015). It was important for me to notify student
affairs, faculty, counseling, and wellness staff and make sure they were aware of the
research plan and the results. If students were willing to give their time to improve the
culture of mental health, I needed to make efforts to ensure their input was validated by
the college.

Mental health is a topic in which sensitive issues can arise when it is being
discussed (Walden University, n.d.). I asked students about mental health issues such as
chronic depression, anxiety, and suicide, which can be emotionally triggering. It was
important for me to think through possible issues that may have arisen and make sure
support options for students were provided at the time of the interviews.
Significance
The rates of students indicating they had depression or are suffering from
depression are increasing in Minnesota (University of Minnesota, 2015, 2017, 2019) and
are not uncommon in higher education (Vidourek & Burbage, 2019). There is a stigma
associated with mental health issues; although it may be decreasing, it is still evident in
the campus culture (Giamos et al., 2017). It is unclear how many students do not finish
higher education due to mental health issues.
The information gathered from this study may provide insight into the mental
health culture in higher education and how it can be improved. Diagnoses such as anxiety
and mental health can impact learning. Education can be an important factor in helping
people reach their goals (Wada et al., 2019). Providing a culture and environment that
supports well-being can be a tool that increases students’ effectiveness and happiness
while reaching those goals.
Social Change
There are many opportunities for social change when looking at the mental health
of communities. Understanding mental health results in more opportunities to improve it
for individuals and for the community. The campus where this study took place has a

mental health improvement initiative in place that was informed by this study. Many
higher education campuses utilize resources such as The Jed Foundation, ACHA, and
Healthy Minds. The results from this study may help college campuses improve the
mental health of their students and their academic achievements. The campus where this
study took place exists to educate students so that they can make an impact in the world,
and this is a common goal for higher education: to provide a valuable workforce for the
community. This value reflects the college founders’ wishes that students will be
equipped to make positive changes in the world after graduation. Understanding students’
mental health would allow the college to better serve the students, would improve the
quality of community, and would allow the students to make positive social change in the
world. One important aspect of higher education is to encourage students to be fully
capable of fulfilling their goals and make positive change (Thomas et al., 2009). This is
an important perspective because it can help motivate people if change agents can figure
out new ways to get them involved.
Summary
This chapter outlined the qualitative study using semistructured interviews and
artifact collection to understand students’ beliefs, perceptions, and experiences about
mental health and how that relates to the culture of the college. This chapter summarized
the study, the background behind it, and its relevancy. Chapter 2 provides an in-depth
literature review of research on mental health and higher education. Chapter 3 outlines
the methodology, Chapter 4 provides the data collection and analysis, and Chapter 5
includes recommendations based on the research.

Chapter 2: Literature Review
This review addresses mental health and how it is viewed and manifested within
college students, recognizing it is just one facet of a whole. Core tenets that rose up after
reading through the literature were threefold: First, the stigma surrounding mental health
still exists, and the collective knowledge around mental health remains problematic to
improving or eliminating the stigma throughout the population and specifically within
higher education. Second, maintaining health (both mental and physical) is
multidimensional, and obtaining improved population health is more successful when
prevention is focused on utilizing cultural, gender, and racial perspectives. Third, health
is addressed from a positive perspective (compared to only when people are ailing or
need help, which can be detrimental). Mental health is seen as something people all have
with variation throughout their lifetime.
Chapter 2 begins with the strategy that was used when reviewing the literature. It
then gives a brief history of mental health and definitions to put the literature review in
context. The theoretical and conceptual frameworks are then described. The review then
focuses on current trends that are occurring in higher education, with the pandemic, and
the increased utilization of online education and studies on how these are impacting
mental health. Next, culture is reviewed in relationship to mental health, followed by the
concept of belonging. The stigma related to mental health in general is then reviewed.
Research conducted on the attitudes and beliefs surrounding mental health is summarized
next. Substance abuse, treatment barriers, and current study considerations related to
mental health conclude this chapter.

Literature Search Strategy
Research questions were developed and key terms from those questions were used
for the literature searches. Searches were done over time to include relevant topics. For
example, I included research that was done on the mental health impacts of the pandemic
on college students. Because the pandemic was recent and the impact is ongoing, research
was limited, but there were some studies that had been published, and these are included.
Primary terms that were used included mental health, culture, and higher education.
Research questions and a tree of topics and terms that were used in the searches are
included in Appendix A. A detailed list of searches, the library databases, and the search
engines used are also included in Appendix A.
Initial Exploration Literature Review
The articles reviewed were selected because they related to mental health on a
college campus and were used for initial exploration to choose the topic and development
of this study. The keywords searched were culture, mental health, anxiety, depression,
stress, college, higher education, and university. The main search tool used was the
Thoreau multi-database. This initial literature review indicated that more could be learned
about mental health in the higher education setting.
Brady et al. (2018) investigated causes of anxiety or worry and how this worry
could be reduced by increasing the amount and type of preexam communication.
Academic-related mental health issues appear to continue to be an issue in higher
education. Denckla and Bornstein (2015) found that there are some advantages and
disadvantages to attachment and detachment strategies when dealing with stress. Denckla

and Bornstein found that understanding the student situation was key in determining
which strategy to use. This can be important with the traditional college student because
they are detaching from the home they grew up in and adjusting to a more independent
life.
A study by Giamos et al. (2017) resulted in insight into the stigma associated with
mental health and useful information for future programing. This study included a novel
interview process that was useful in gaining hard to gather information. This interview
process was reviewed for the data gathering process of the current study. The Giamos et
al. study was also used to develop the process for the qualitative methods used in the
current study.
Hasan et al. (2017) found that issues regarding sleep, anxiety, religion, and
emotional adjustment are related and can impact mental health of university students.
Orzech et al. (2011) also showed a direct connection between trouble sleeping and the
existence of mental health issues or conflict in a relationship. This research added
understanding regarding the connection between sleep and mental health. The culture in
higher education and academic pressure often results in students limiting sleep as they
work to study for tests or complete homework.
Newton and Ohrt (2018) found opportunities to use mindfulness-based
interventions such as meditation in support groups with students dealing with grief,
anxiety, and depression. Rankin et al. (2018) found that students with strong social
support were less likely to report depressive symptoms. This connection could relate to
how mental health issues are communicated with the community. Rahn et al. (2016)

reviewed the ACHA’s National College Health Assessment and found limitations with
the survey that can be important in utilizing data from this source. Rankin et al. (2018)
found that students with strong social support were less likely to report depressive
symptoms.
History of Mental Health, Physical Health, and Higher Education
The health industry has focused mostly on physical health, and in the United
States the focus has been on illness diagnosis and intervention. Technology and acute
care are overused to the detriment of public health, prevention, and primary care (Shi &
Singh, 2019). The WHO (2020) defined health as the well-being associated with the
mental, physical, and social aspects of an individual and how overall health can be
optimized when attention is multidimensional. In considering health and well-being, it
can be difficult to make an intervention to improve the health of a population if all
aspects (e.g., mental, physical, spiritual, and social) are not considered.
Mental health as a medical field came into existence around the same time as the
WHO developed the definition of health in 1948 (Bertolote, 2008). In 2004, the WHO
published a report promoting mental health defined as “a state of well-being in which the
individual realizes his or her own abilities, can cope with the normal stresses of life, can
work productively and fruitfully, and is able to make a contribution to his or her
community” (p. 13). Although this report was published almost 2 decades ago, provider
and payment practices related to illness and crises remain primary in the United States,
with prevention and promotion as secondary in importance (Shi & Singh, 2019), and the
recommendations of this report are largely unmet.

Similarly, college campus health services have been more focused on the physical
health of students. This has changed with the increasing number of students who have
reported having mental health issues such as depression and anxiety (ACHA, 2019;
Healthy Minds Network, 2023; University of Minnesota, 2019). Although mental health
counseling may be available at many colleges, accessibility continues to be an issue. This
can be due to confusion about services, payment, and/or stigma regarding mental health
(M. Shea et al., 2019). Larger, public universities with less access to resources appear to
have higher rates of mental health issues (Ketchen Lipson et al., 2015).
Traditional college students, approximately ages 18–22, are a unique population in
their transition to adulthood. College rules can dictate that they must live on campus,
which results in a semiclosed environment where students live, eat, go to school, and
sometimes work together. This type of environment can also impact all aspects of their
health. Smaller, private campuses with on-site housing appear to have lower rates of
mental health issues (Ketchen Lipson et al., 2015). The community created by academics
and residential requirements can also be an opportunity for encouraging lifelong healthy
habits and behaviors that can improve the health of students.
Attention to mental health can be crucial in adolescence because it can establish
the precedent for the future. Students can have the onset of mental health issues starting
in college, so it can be difficult to determine if issues will be chronic or episodic (Condra
et al., 2015; Ketchen Lipson et al., 2015). Campus culture can support all types of issues
when viewed holistically. The college-age student population is important to look at
because changing the trajectory of mental illness at this point can have lifelong

implications (L. Chen et al, 2013; Y.-I. Lee et al., 2019). Even though 3 out of 5 students
experience anxiety and 2 out of 5 experience depression, only 10%–15% accessed
counseling services on campus (Roy, 2018). These numbers are increasing and have been
exacerbated by the pandemic. Improving individual and community health requires a
systemic and cultural change that posits mental health as a campus-wide responsibility
and that health and well-being are shared values for the entire community, including
students, staff, and faculty (Roy, 2018).
It can be beneficial and more accurate to consider mental health as a continuum.
Traditionally, mental health was not considered unless someone became ill or was
struggling. The mental health continuum model (MHCM) by Keyes (2002) categorized
individuals into languishing, moderately mentally healthy, or flourishing. The idea is that
people are not well or sick; they are often somewhere in between and somewhere
different on the continuum. Optimal mental or physical health is an elusive target and is
individualized with each person. As with physical health, mental health exists on a
continuum, and the stigma can be decreased by increasing the understanding that
everyone is on this continuum (Persson et al., 2021; Peter et al., 2021). Also, an
individual’s understanding of this continuum and where they are on the scale is hoped to
improve awareness and coping strategies.
Another MHCM was developed by the Canadian Department of National Defense
(S.-P. Chen et al., 2020). This model addresses the continuum of health from well to ill,
gives indicators for each stage, and gives recommendations for how to maintain, improve,
or treat mental health depending on where on the continuum a person falls.
Although there are differences between how points along the continuum are named in the
MHCM developed by the Canadian Department of National Defense and the MHCM
developed by Keyes, the similarities are a focus on wellness and that all individuals are
moving along the continuum in the course of life.
Theoretical Foundation
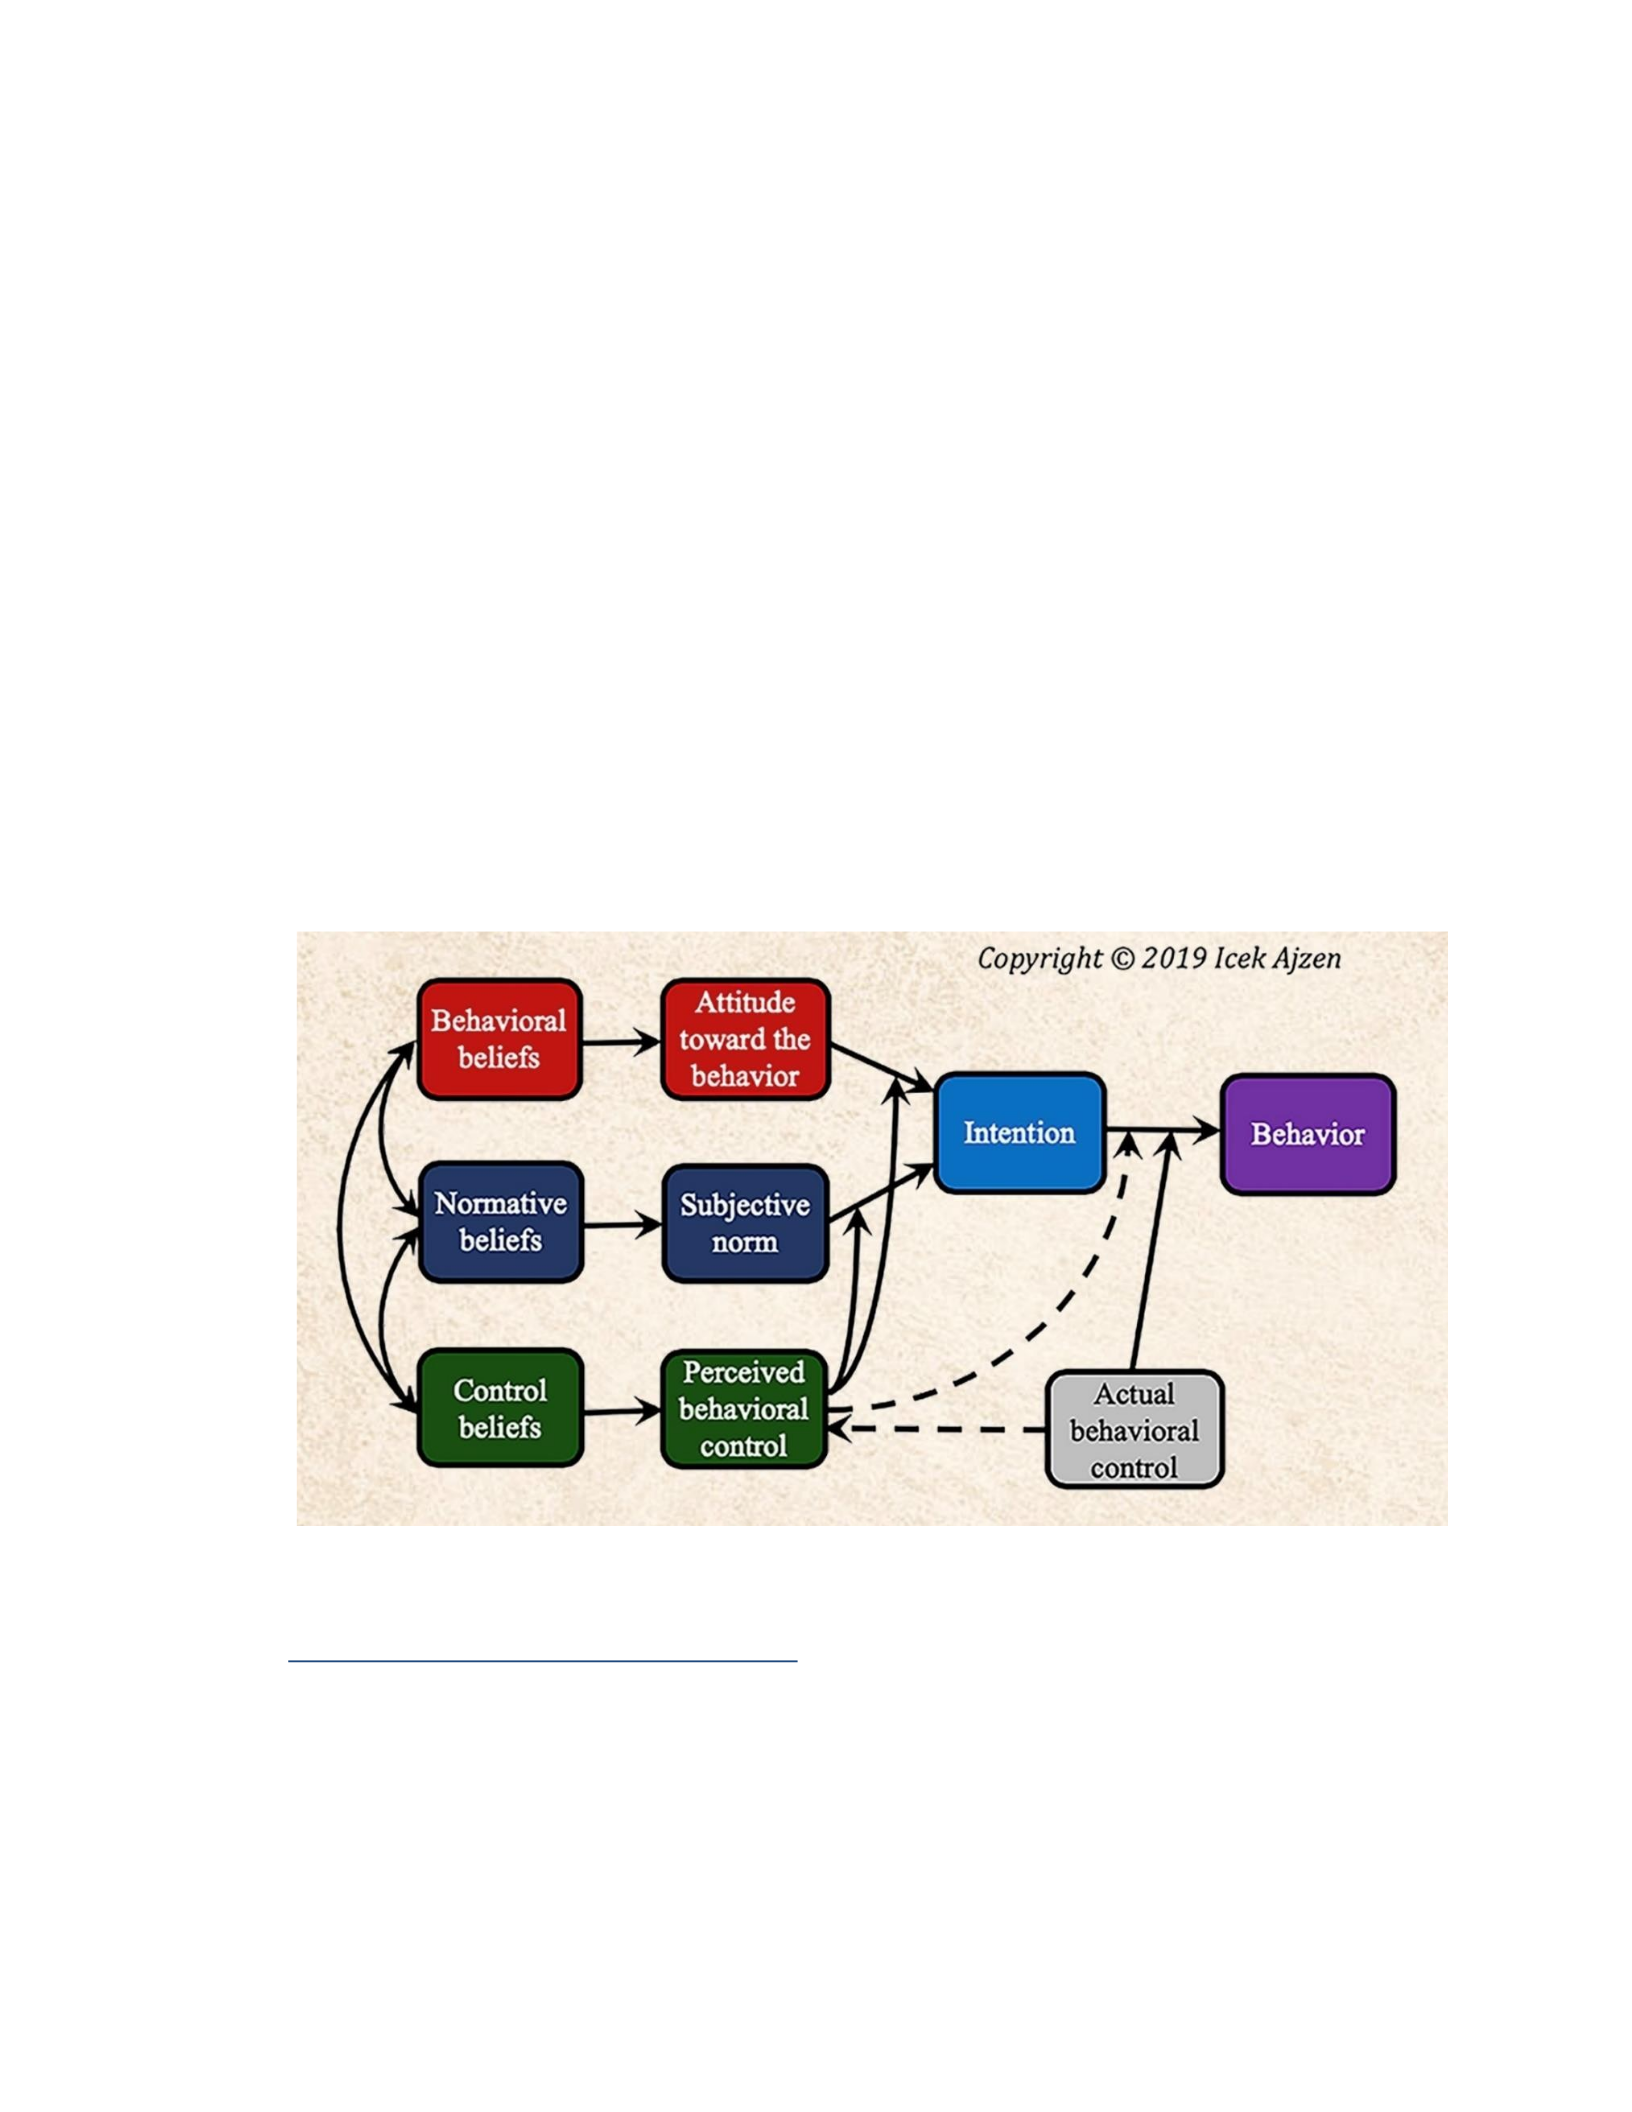
The theory that was used for this study was the TPB (see Figure 1). This theory
was created by Ajzen in the 1980s and was refined in the following years (Ajzen, 1991).
Figure 1
TBP Diagram
Note. Adapted from I. Ajzen, University of Massachusetts, Amherst.
https://people.umass.edu/aizen/tpb.html, Copyright © 2019 by Icek Ajzen.
The premise of this theory is that an individual may have an intention to behave in
a certain way, and this intention is impacted by what the subjective norm is, the

individual’s attitudes regarding the behavior, and the individual’s perceived control over
the behavior. In the current study, the model was used to explore students’ understanding,
experiences, and attitudes about mental health for themselves, for the campus community,
regarding help seeking, and how the culture of the community impacts overall mental
health and help seeking. The model has three main constructs related to behaviors,
normative beliefs, and control and were defined by Ajzen (2021) as follows:
Behavioral beliefs are defined by whether students believe an action will produce a result.
Normative behaviors and the subjective norm relate to the social pressure or peer pressure
to behave in a certain way. In this case, when students move on campus, they are exposed
to cultural rules about acceptable behavior. The beliefs related to the control construct
have to do with what students feel is within their ability to control.
M. Shea et al. (2019) used the TPB to study barriers to treatment seeking for
mental health issues. M. Shea et al. looked at students’ thought processes regarding help
seeking and the associated behaviors. One issue discovered was a negative association
between value and intention to seek help from mental health counseling. It was thought
that increasing students’ knowledge regarding counseling could help with this issue.
Cultural barriers were also found, indicating more diverse counselors could increase help
seeking. M. Shea et al. focused on the barriers present when students have a need for help
or are experiencing mental illness.
J. I. Chen et al. (2016) also focused on mental health help-seeking intentions. This
study focused on the connection between the campus culture and help-seeking intentions.
The findings from this study connected perceived campus culture with community-held

treatment beliefs. J. I. Chen et al. suggested that future studies could incorporate overall
cultural perceptions into planning for programs and services related to mental health.
Current Trends About College Students and Mental Health
Higher Education and Mental Health
Research focused on mental health in higher education addressed current trends
across the United States. Higher education institutions have used a health survey
investigating all components of health including physical and mental conducted by the
ACHA called the National College Health Assessment. This survey showed a growth of
the prevalence of lifetime depression diagnosis from 10% to 20% between 2000 and 2015
(ACHA, 2001, 2014). The trend was more pronounced for students reporting generalized
anxiety, social anxiety, and depression. The research by the ACHA is consistent with
college-level research on health at the campus where the current study took place. Data
showed increasing numbers of students reporting that they had been diagnosed with
anxiety or depression within their lifetime. The ACHA (2014) assessment also noted that
there were increasing numbers of students seeking treatment. Recent data tracked at the
campus where the current study was conducted also showed an increase in counseling
services needed, particularly crises-oriented services (Student Health and Wellness
Director, personal communication, February 7, 2020).
Students with mental health issues are more likely to drop out and not complete
their degree (Baik et al., 2019). Baik et al. surveyed a large sample of students and found
that mental health is an increasing concern. Student recommendations for addressing the
issue focused on many areas including teaching practices, student services and support,

culture, and student activities. Student dropout and continuation of higher education is
also likely impacted by the pandemic.
COVID-19 Impact
The impact of the coronavirus pandemic is multifaceted. Although some
individuals were directly affected when they contracted the virus, others may have
ongoing mental health issues due to isolation and changes in social activities. Higher
educational institutions need to be aware of mental health issues and intentionally work to
address issues (Zhai & Du, 2020). Along with providing support, this includes educating
and empowering college students to address their own issues. Social support or sense of
community can decrease the likelihood of anxiety and is more difficult to consistently
achieve in a pandemic (Fu et al., 2020). Fu et al. also found reports of increased anxiety
in college students who reported decreased economic status. A qualitative study
conducted by Son et al. (2020) found the concerns that were most often reported were
worry about health of themselves and loved ones, along with difficulty concentrating.
Students tended to be more worried about others versus themselves getting sick and
having resulting economic ramifications; but they were more concerned about their own
educational opportunities or situation (Cohen et al., 2020). The ability to concentrate can
have a direct effect on students’ ability to complete coursework. Developing appropriate
and effective coping mechanisms can be important in dealing with long lasting anxiety
and depression.
Newer methods for maintaining health (including mental, physical, social, and
spiritual) have gained popularity, for example, meditation or mindfulness apps such as

Headspace. Headspace’s co-founder Puddicome noted that the issues that people struggle
with are similar to what they have been in the past, they are just amplified by the issues
surrounding the pandemic (Lindsay, 2021). Headspace has produced some materials for
Netflix which is one social media tool that has become integrated into popular services.
Other meditation, yoga, and mindfulness exercises can be found on free or purchased
phone apps, health insurance and employer wellness pages, YouTube, and the internet.
The MHCM by Keyes was used as a theoretical framework to look at college
students’ well-being during the initial lockdown during the COVID-19 pandemic in
spring of 2020 (Capone et al., 2020). Capone et al. (2020) found that there was a negative
impact from the initial lockdown during the COVID-19 pandemic and recommended
using the results of their study to improve college students’ well-being going forward. A
focus on the well-being of college students and helping them learn how to put together
their own set of resources can help them cope in the future.
Online Teaching Issues
Online teaching has become more prevalent, even before the COVID-19
pandemic, but especially after it, creating ramifications for teachers. Addressing mental
illness or difficulties may not be in teachers’ repertoire and the inability to physically see
the students can add one more factor that makes any intervention difficult (Holt et al,
2019). It can be important for schools to have a support structure of services and
resources for faculty along with teachers understanding their role as a professor (not a
clinician) (Holt et al., 2019). Students struggled with the weight of workload, pace of
work, and not being able to concentrate in online classes during the COVID-19 pandemic

(Son et al., 2020). Holt et al. (2019) strongly advised that faculty be able to identify
online issues and be aware of and able to provide helpful and easy to use resources.
Providing links to these resources within the class and on the syllabus may also help
students. The shift to online teaching creates a different environment that needs to be
addressed.
Culture and Mental Health Issues
Culture needs to be considered when planning mental health interventions and not
only the culture of the location or community that you are working with, but the
subcultures (e.g., gender, race, age, etc.) within that community (Mokkarala et al., 2016).
The relationship of culture to other concepts such as belonging, social aspects, habit
development, engrained values, etc. is complicated and interwoven. Xu (2020, p. 522)
stated, “...there forms an invisible centripetal force attracting the students’ behaviors to a
common cultural spirit, promoting their individual socialization, which plays an
important role in the healthy growth of college students’ physical and mental health.”
Culture is a foundational concept that can be altered in ways to improve health.
Perceptions regarding mental health and illness can differ due to cultural
perspectives that are related to cultural learnings versus data. For example, in 2020-2022
the United States was struggling with immunizing against the COVID-19 virus, even
though scientific data demonstrated effectiveness (Mann et al., 2022). Another example is
that the benefits of mental health counseling are scientifically valid, and people do not
access these services (Downs & Eisenberg, 2012; Kuhlman et al., 2019). Effective

interventions depend upon a good understanding of how and why social norms within
each subculture impact the effectiveness of the intervention and the plan to implement it.
This can be especially true for cultures that have been historically attacked or minimized.
Revitalizing and recognizing cultural experiences that have been lost can lead to
enhancement of academic achievement (H. Shea et al., 2019). Understanding cultural
values can help you determine how they will act and what interventions will work best
(Liang et al., 2017). For example, most students may not go to counseling initially. They
will need to be continually encouraged. They conform to norms which would be
managing your mental health on your own (Kuhlman et al., 2019). How can this be
shifted to a more communal, help one another approach?
Mental health issues such as anxiety and depression are increasing in prevalence
among college students. The ACHA (2019) survey showed that 3 out of 5 students
suffered from high anxiety and 2 out of 5 suffered from depression. A small percentage
(less than 25%) sought help from campus health services, although the majority of
students were most likely to look to their friends or peers for psychological help (ACHA,
2019; Kuhlman et al., 2019; Roy, 2018). Kuhlman et al. (2019) found that students with
more serious mental health issues were less likely to participate in peer-helping
behaviors. Issues with mental health can impact friendships and socialization as well as
their physical health (S.-P. Chen et al., 2020).
The culture of students, their interactions with each other, and communication
about mental health can be complicated. Often, students can be seen as successful in

many ways - academically, socially, athletically, artistically, etc. - but below the surface
they are struggling (Wieland et al., 2020). This contrast is exacerbated by the positive
picture displayed by social media. The University of Pennsylvania (2018) started a
resiliency and story sharing site that worked to highlight stories from the campus
community including staff, faculty, and students. Multidimensional prevention efforts are
effective if strategies not only target individual components, but community aspects such
as interpersonal and campus culture including attitudes, behaviors, and policies (Downs
& Eisenberg, 2012; Y.-I. Lee et al., 2019). Including students in the planning to
determine the needs for changing the culture is important (Giamos, et al., 2017).
Perceived campus culture was against receiving counseling services and supported
an ongoing stigma associated with mental illness (J.I. Chen et al., 2016; Henderson, et al.,
2018). Giamos et al. (2017) had similar findings from their study and noted that changing
the infrastructure of mental health services and improving access could increase their
utilization. The United States has a more individualistic culture compared to other
countries (such as the Scandinavian countries or Japan which have more collective or
interdependent cultures) (Kuhlman et al., 2019). Individuals were okay with others
having mental health, issues but felt others wouldn’t be okay with their own mental health
issues (Carmack et al., 2018; Giamos, et al., 2017). The complications within the mental
health arena can be related to other societal or behavioral problems as well and these can
be ignored with the individualistic cultural orientation (Y.-I. Lee et al., 2019). One way to
address this reticence to obtain treatment is to educate students about the mental health

continuum and the focus on having the presence of positive emotions and developing
resiliency (S-P Chen et al., 2020).
J. I. Chen, et al. (2016) used the TPB to explore how the climate or culture of a
college campus can impact help-seeking behaviors. If students, faculty, or staff talk about
difficulty in getting appointments with counseling services, or that appointments are
ineffective, the resulting culture may be to not attempt to schedule appointments.
Additionally, if students are getting the message that people who seek counseling are
weak or not able to academically perform, then students may shy away from seeking
counseling service appointments. This can shift help-seeking for mental health issues to
be more informal between individuals, which often means students with mental health
issues helping others. There may be benefits to this, but it can also lead to unresolved and
heightened issues. Race and gender can also have an impact on mental health helpseeking
behaviors. It can be important to understand the differences that exist in subpopulations
or cultures to determine how to increase utilization of counseling services (Liang et al.,
2017). Rates of students reporting anxiety and/or depression have increased to be the
majority of college students (ACHA, 2019). It is hard for students to differentiate
between having a clinical problem and intermittent issues with depression or anxiety
(Carmack et al., 2018). Thus, making an appointment with counseling services is
important.
The vast majority of students (over 80%) who die by suicide never accessed
counselors at their school’s mental health clinic (Ketchen Lipson et al., 2015). Ketchen
Lipson et al. studied undergraduates who participated in the Healthy Minds Study from

2007 to 2013. Ketchen Lipson et al. (2015) also reported that only 39.4% of students with
mental health problems received treatment. Ketchen Lipson et al. (2015) found that
mental health problems appeared to be more prevalent at campuses where mental health
resources were limited. They also found that students with mental health issues were
more likely to have academic performance issues.
The U.S. healthcare system has predominantly and historically focused on
intervention and downstream issues (Shi & Singh, 2019). Creating effective change with
upstream preventative approaches is equally important (Gardner & Kerridge, 2019).
These approaches can be related to health practices such as exercise, meditation, healthy
eating, and good sleep patterns. When these changes become the norm, they also become
an integral part of the culture.
The National Alliance for Mental Health (n.d.) noted that the transition into
adulthood takes place on the college campus. There are many choices that need to be
made regarding the school you go to: such as who you will live with, your major, and
what extracurricular you will join. There are important steps to take that can help a person
with mental health issues get assistance. For example, they may get time and one half on
a test or three extra days to complete it.
The academic culture on the college campus can also impact mental health. Wada
et al. (2019) found that at the university they studied there was a focus on ability that led
to mental health concerns. This focus on ability or developing excellence in knowledge
and skills can often mean neglecting sufficient focus on well-being (Lambert et al., 2019).
Students that need to accomplish or achieve to be able to maintain their academic status

can have diminished joy and increased stress. This culture of achievement versus a love
of learning could be explored to determine the impacts on mental health. One idea
suggested by Condra et al. (2015) was to have a department faculty liaison to mental
health services. This faculty member could provide assistance to other faculty as they
deal with mental health issues. Another idea was to create more academic opportunities to
learn and practice wellness activities and how they can benefit overall lifelong wellbeing.
Lambert et al. (2019) found there to be benefits of doing this in a culturally diverse
college. L. Chen et al. (2013) found that students that were more satisfied with their
academic major reported less depressive symptoms. Effectively advising students can be
important to make sure appropriate counseling is given to students as they choose an
academic path.
In higher education, the imposter phenomenon can exist. Cokley et al. (2017)
defined imposter phenomenon as a condition where people feel that they don’t really
belong or are not worthy of their accomplishments, even when they are worthy. The
phenomenon can be instigated by social cues. The feelings of otherness and intellectual
incompetence can be linked to poor mental health (Cokley et al., 2017).
Having a strong sense of life purpose and resiliency can ameliorate racial/ethnic
stressors (Hong et al., 2018). The sense of belonging: to a college community, to a home
community, to a family, to a high school, to an ethnic group, to a team, etc.; is
multifaceted. Can it help if you have a strong sense of belonging somewhere even if your
sense of belonging is low in another area? For example, if you have a strong sense of

belonging in your family but not on the college campus do you still do okay and treat one
as your “home for belonging needs?”
Hernández and Villodae (2020) reported that there may be some buffering impact
on mental health if one has a strong sense of belonging to their ethnic or racial
community. Military-connected students are also a population of students that can have
increased and/or notable issues with their mental health. This does not necessarily mean
that all military-connected students will have mental health issues, but that they are at a
risk for them and the issues they have can be more severe (Bonar, 2016). Bonar (2016)
recommended targeted strategies to make sure individualized support services were in
place for military-connected students. Mental health strategies were overlaped with other
strategies for improving health and wellbeing, for example, providing cultural training
and improving communication and connections with available services. Veterans were
less likely to seek help related to their mental health, particularly within the educational
community and more likely to practice avoidant coping (Romero et al., 2015). Increasing
familial social support and combining with other problem-focused coping methods can
help reduce depressive symptoms (Romero et al., 2015).
The sense of community and its relationship to the overall college campus culture
can also be a factor in mental health culture. The Caring Project (2018) utilized a
community empowerment philosophy with its traditional college students for problem
identification, dialog and solution seeking, ownership of the plan, and future actions. This
project started with a broader focus that included mental health and substance misuse but

narrowed its approach to alcohol misuse as that was the most pressing issue (Stuart et al.,
2018). The project wasn’t punitive but addressed the issues with dialog and prevention.
Another angle that impacted the overall culture of a higher educational
community was the blending of cultures that students brought with them. For example,
international students can struggle to acclimate to the college’s culture which can result in
mental health issues. Amado et al. (2020) found that identity gaps experienced by
international students were associated with stress and depression. Stress was defined as
acculturative stress which is specifically related to the process of adjusting your sense of
being to the new environment around you (Amado et al., 2020). Corona et al. (2017)
found that when acculturative stress and discrimination increases, mental health issues
increase. When mental health issues increase, there was lower academic achievement,
success, and completion. Corona et al. concluded that helping Latinx students in
particular keep their connections with family and culture strong, it helped improve mental
health. A poor parental relationship has also been found to be correlated with mental
health issues (L. Chen et al., 2013). Strong family support can minimize issues with
depression, stress, and anxiety. Colleges can ensure that their student support staff are
effectively trained in supporting mental and physical health issues. For example,
residential advisors (RA’s) can visit the counseling support centers for a tour and training,
so they understand how the services work (Canto et al., 2017).
Athletes have unique perspectives when looking at mental and physical health.
Lundqvist and Andersson (2021) conducted a narrative review of theoretical perspectives
concerning mental health and athletes. Lundqvist and Andersson stated that the topic of

mental health is complicated, and sports psychology has not reached a consensus in its
definitions. For example, there were several different models considering health on a
continuum versus a solid state and disagreements about how the ideal model should look.
Research in the athletic realm looked at emotion-related feelings (e.g., anxiety, stress) and
how they can be intermittently and naturally present as part of competition. These
emotions and feelings that may be natural for an athlete may be a concern for a nonathlete
or outside of the competitive environment.
First-generation college students tended to underutilize social support so as not to
burden others and to develop a need for self-reliance (Chang et al., 2020). Eveland (2020)
noted that there is a gap in literature exploring the causes behind differences that can be
found with first-generation college students. They can find implicit support by just
hanging out with others. There can be intersectionality between social group
identification which can complicate how they look at mental and physical health and
illnesses (Chang et al., 2020). Eveland (2020) found that first-generation college students
may receive less social support from campus-activities. This may be due to the increased
possibility they don’t live on campus and accessed campus resources differently.
Culture of Belonging
Part of the college experience as an 18-year-old was to sever the dependence on
the family and people one grew up with and develop a new or enhanced sense of self
(Capone et al., 2020). One of the factors of the self-determination theory is defined by the
need to belong (Grevenstein et al., 2019). The relationship between well-being and
belonging is an important one to consider (Capone et al., 2020). Well-being and

belonging can lend themselves to better academic success. Having good family
relationships can be directly related to self-efficiency and resilience (Grevenstein et al.,
2019). A sense of belonging was found to be linked to positive mental health and lower
alcohol misuse (Henderson et al., 2018). This study also found that the role that
professors and staff play regarding belongingness can have an impact on alcohol misuse.
The transition from living as part of a family to living independently may be
impacted by the feeling of belonging in the family unit. Brené Brown (2017, p. 31) define
belonging as “the innate human desire to be part of something larger than us.” The
process of becoming part of one’s college community can be a struggle with peer
pressure and looking to others for approval. Brown noted that to effectively belong, one
needs to present their real and authentic self. Authenticity is when one is able to be honest
and real about who they are and are able to comfortably present that being to others in
their community (Myers, 2011). Part of this authenticity as a college student was
determining what one wants to be when they are done with college. There can be conflict
between what others want, what is expected, and where an individual finds their true
passion. This true passion can be reflected in one’s authentic self. Pisarik and Larson
(2011) hypothesized a relationship and the results to their study found a statistically
positive association between measures of authenticity and measures of psychological
well-being for college students. This was supported by previous work by Erickson (1968)
and Harter (2002).
First-generation college students can have some unique struggles with
belongingness and fit on campus if they came from an environment where college was

not the norm (Chang et al., 2020). This can also be true for other minority segments of the
college population. If college students are seeing their differences or otherness more
clearly than their acceptance and role in the community, it can impact feelings of
belonging. It can be difficult to create a culture of belonging in a diverse population
(Chang et al., 2020; Hernández, & Villodas, 2020; Hong et al., 2018).
Communities are defined by the relationships within them. Bowen family systems
theory outlined the way anxiety and stressors were managed in these relationships
(Frederick et al., 2016). When one person is having negative health issues, they may look
to another person in the community for support. The support person then relies on another
person to help relieve the stress of caring for another individual. Keyes (2007) noted that
having a sense of belonging within the community is one of the dimensions of mental
health. S. Lee et al. (2016) found that the cultural capital and a strong sense of community
that existed at a college can have an impact on life satisfaction, social support, and
general well-being on the campus. Procentese et al. (2019) found a connection between a
sense of community and the sense of responsible togetherness. If people feel connected
and part of the community their relationships within that community will be stronger, and
actions they take to support others will be more impactful. The WHO (2020) definition of
health includes physical, mental, and social aspects. Keyes (2007) connected this up and
noted the importance and interconnectedness of all three legs of the stool. The COVID-19
pandemic indicated the health effects of isolation and not being able to interact with
others in the community which is the social aspect of health.

Stigma and Mental Health
One issue with mental health is the associated stigma. Understanding the
components that result from the stigma can help with conceptualization (Link & Phelan,
2006). These can be summarized by how humans see differences between people, which
results in labels or stereotypes. This can be considered a moral experience or career which
means societies ability to categorize people based on societal beliefs that may be acted
out in intentional ways or subconsciously (Goffman, 1963; Harvard Medical School,
2010). The term “career” recognizes the long-term existence of some stigmas and that an
individual experiences some stigmas for a lifetime (Goffman,1963). This labeling further
categorizes and separates people unnecessarily and inaccurately into an “us” and “them
(Goffman, 1963).” People with mental health issues then face discrimination and loss of
power. It is not accepted and recognized that everyone has mental health and at any point
in time it is possible for an individual to have struggles with the quality of that mental
health.
Link and Phelan (2006) noted the difference in public reaction to an individual
with a broken bone or heart disease compared to schizophrenia or AIDS. This stigma can
lead to discrimination, lack of available resources, and avoidance of existing resources.
Discrimination towards individuals experiencing mental illness can be direct, structural,
or insidious. For example, structural stigma can partially explain governmental research
funding decisions (DeLuca et al., 2017). This stigma may impact mental health treatment.
Insidious types of discrimination are often incorporated and integrated into the culture
which makes them not only hard to see, but hard to change.

Using the MHCM as a foundation to communications surrounding mental health
can help to reduce stigma (Peter et al., 2021; Smith & Applegate, 2018). Framing mental
illness as something that everyone experiences at some time can help to create more of an
inclusive experience when people find themselves struggling. Society tends to view
physical health from a positive starting point and mental health from a negative starting
point (Weber, 2021). These differing perspectives of physical and mental health lead to
the stigma associated with mental illness. They also lead to the lack of treatment that
many are willing to get as they don’t want to be designated with a mental illness.
Dialectical thinking, which refers to the ability to see things from multiple
perspectives, can be helpful to broaden the view and allow for more solutions (Yang et
al., 2016). Yang et al. (2016) also noted that this more complex observation along with
experiencing more emotional complexity can also benefit physical health. Eisenberg et al.
(2012) surveyed college students to determine if they held beliefs or attitudes that
prevented them from going to a behavioral health counselor. They found there were not
any differences in views and opinions on counselors whether college students had chosen
to go to one. College students with mental health issues that did not go to a counselor did
not appear to have any expected negative feelings about therapy (Eisenberg et al., 2012).
College students’ reasons for not going to a therapist included not feeling their problem
was serious enough, independence, not feeling their problem warranted counseling, or
they did not feel they had time (Downs & Eisenberg, 2012). Dillinger (2021) reported
that adolescents with high rates of stigma themselves, were less likely to help others than
those with low stigma rates. These peer-helping relationships may be improved with

effective messaging that target culture changes and addressing gender differences in
supporting peers (Kuhlman et al, 2019).
Wada et al. (2019) found that the stigma and academic achievement culture were
intertwined. If college students’ mental health impacts their ability to complete the
workload, the perception of their academic ability was altered. The focus was on college
students with ability – mentally, physically, and academically. Mental health disabilities
can be viewed as an inability to achieve academically. Higher education is about
academic achievement and a stigma surrounding one’s ability to consistently and
naturally achieve can be limiting.
According to Goffman (1963), there are two forms of stigma – self-stigma and
social stigma. Self-stigma is prejudicial feelings towards mental health illness in yourself
(Goffman). Social stigma is looking outward towards others and feeling prejudicial
regarding their mental illness or ill-health (Goffman). These two types of stigma can
impact how individuals personally make decisions or attend to their mental health along
with how they provide support to others.
The stigma can be supported inadvertently by professionals in the field. Canto et
al. (2017) begin their article regarding college students in mental health crises by
highlighting recent campus shootings. Canto et al. continues the article with many
important points about the changes college students were going through and discuss the
range of mental health issues and how residential advisors can be important in prevention
efforts. In reality, a shooting or injuring someone else’s life is a remote chance versus the
very present and very prominent mental health issues that are impacting the majority of

college students (and on campuses where no shootings or adverse incidents against other
students have occurred).
Stigma was found to be more effectively eliminated with contact-based programs
such as face-to-face presentations (Corrigan et al., 2014; Y.-I. Lee et al., 2019; Ma et al.,
2018). Important components of presentations included having presenters with lived
experiences and stories. It can be important to incorporate cultural considerations into
these stories as the effectiveness of the message is different depending on the audience
(Ma et al., 2018). Ma et al. (2018) also noted the importance of effective narrative to
transport the individual into the story to allow for the listener to connect with the
storytellers’ experiences. Efforts to utilize individuals as experience and story sharers
needed to be carefully designed and implemented to avoid creating any residual stigma
around the individuals that were brave and vulnerable in sharing their stories (Smith &
Applegate, 2018).
It can also be noted that the stigma around other positive health measures such as
meditation, exercise, and a good diet is low and yet it can be difficult to get people to
make effective changes with these measures (Eisenberg et al., 2012). There can be a
social aspect, for example, if others are participating in healthy behaviors, it may assist
their friends. The current societal culture has a strong element of immediacy towards
results with quick access to information and needs through social media and internet
connections. Developing healthy habits may not have this same immediacy, which can
cause a disconnect and hamper people’s ability to firmly establish healthy habits.

Attitudes and Beliefs
An ongoing issue with mental healthcare was that people were unlikely to receive
treatment (Eisenberg et al., 2012; Weber, 2021). Weber (2021) noted that public
perspective towards mental health care tends towards the negative, compared to physical
health where perspectives were more positive related. Treatment can mean addressing
issues with an individual’s primary care physician or accessing an individual specializing
in mental health counseling. College students often have counseling support on-campus,
but it can be underutilized. Eisenberg et al. (2012) found that college students’ attitudes
and beliefs about mental health treatment were fairly positive. Eisenberg et al. (2012)
compared mental health treatment to other positive health behaviors such as eating
healthy and exercise. Even though these behaviors do not have a similar stigma related to
them, it can still be difficult to get people to form healthy habits related to them.
Encouraging effective treatment methods such as counseling in adolescents or traditional
aged college students can be important as it can decrease mental illness progression and
prevent more serious issues such as death from mental illness (Eisenberg et al., 2012).
Studies have found that a minimal number of college students that die by suicide contact
the college counseling center (Downs & Eisenberg, 2012; Son et al., 2020).
Beliefs in a higher being or ideas about spirituality can also impact mental health.
Klausli and Caudill (2018) found that the risk for depression was similar for college
students whether they were within a religious environment or not. Klausli and Caudill
found in their literature review, the results were mixed. They concluded that even if
depression is relatively equal, the focus on spirituality and its messaging may make the

pathway to and recovery from depression different. The meaning that college students
may attribute to their feelings may be shifted by the communication and thoughts related
to why and how humans exist. Higher levels of ability to cope and reduce stress were
found to be related to higher levels of quality of life related to spiritual growth, exercise,
healthy eating, and social support. (Roming & Howard, 2019).
The MHCM refers to all individuals having mental health somewhere along a
continuum and not a dichotomy which is often commonly assumed (Persson et al., 2021;
Peter et al., 2021). Weber (2021) wrote that beliefs, that can often be unconscious, posit
physical health on the positive side initially, any variations as normal, and not usually the
fault of the individual experiencing the physical malady. Alternatively, common thinking
surrounding mental health originated from a negative perspective and more within the
individual’s control (Weber, 2021). From a scientific perspective, the two types of health
– physical and mental – have more in common. The negative view or stigma surrounding
mental health can prevent people from accessing care (Holt et al., 2019).
Mental Health and Substance Misuse
There is a strong relationship between mental health and substance use. Alcohol,
marijuana, or other substances can be used when an individual is having mental health
issues and vice versa. The Caring Campus Project (2018) noted that the issue can lead to
a risk factor perspective, i.e., a student with mental illness may turn to substances for
relief. Substance use can also be a way of self-medicating (Walters et al., 2018) and
perhaps substance use becomes a substitute for counseling. In addition, mental illness can
also result from substance misuse. The Caring Campus Project (2018) developed a

program at a couple universities that centered on college students leading the program. It
explored evidence informed approaches such as college students determining where they
fell on the risk continuum at a given moment and monitoring their own behavior, peer
sharing from college students with experience with mental illness and/or substance abuse,
and student leadership impacting culture change.
Just as mental, physical, and social health is intertwined, mental health can also be
related to other issues such as chemical addiction. Mental health can be linked with
substance abuse both as a consequence of mental health concerns and as a risk factor
leading to mental health concerns (Cohen et al., 2020). Heavier alcohol use can be linked
with marijuana use and the frequency you utilize the substances (Keith et al., 2015). The
findings by Keith, et al. (2015) may be linked to college students who are struggling
looking for multiple ways to chemically ease their mental pain. Another study found
linkages between depression and tobacco, cannabis, and harder drugs (Walters et al.,
2018). College students may be using substances to self-medicate as there was found to
be a positive relationship between depression and substance use. Walters et al. (2018)
noted that research on the connections between mental health and addiction is conflicting
and more needs to be done. Limitations in this study (see Walters et al., 2018) included
participants not showing up on data collection days which may also be related to mental
health or addiction issues. Although the research does not appear to be conclusive, it was
important to consider the influence of alcohol, cannabis, and drug use when looking at
depression and anxiety.

Treatment Barriers
Chang et al. (2020) utilized interviews and focus groups that revealed that
firstgeneration college students were conflicted with self-expression and self-reliance
which led to underutilized reliance on others to cope with any mental issues. A literature
review done by Topkaya et al. (2017) in Turkey found that barriers to treatment fit into
three categories; personal barriers (e.g., specific to an individual), socio-cultural barriers
(e.g., cultural norms), and barriers related to the institution providing the care (e.g.,
counselor availability). Lipson et al. (2021) found cost of care the most important barrier
to care noted by traditional aged community college students. Kuhlman et al. (2019) also
found financial barriers along with perceived need, stigma, negative thoughts regarding
counseling, and benefits.
One barrier was financial reasons (40% of college students cited this in a survey
by Downs & Eisenberg, 2012). This makes it a system failure if the service was available
on campus or was provided for free and college students don’t know that. Limitations on
counselor staff and resources can cause providers to be less open about services and
hesitant about advertising. Often with services that are not charged for, it was felt limits
need to be put in place to prevent overuse.
Some treatments are easier to access than it was in the past, but developing a
routine that utilizes self-help tools can be a challenge. For example, Headspace.com
(2021) has worked with Netflix to develop several tools that can help with keeping
mental health stable in a series called Headspace: Guide to Meditation. Meditation has
been proven to impact not only your emotional state, but physical indicators as well, such

as lower blood pressure on a limited research base. Zheng et al., (2020) found through
empirical cross-sectional and time lagged studies that utilizing mindfulness techniques
may be an effective way to increase well-being. Pisarik and Larson (2011) conducted a
study on first-year college students where they utilized mandalas and assessed well-being
and authenticity. They found that the mandala tool was effective in increasing
selfawareness. Just as encouraging people to exercise and eat healthy comes with its
challenges, so does asking people to incorporate mindfulness techniques.
M. Shea et al., (2019) utilized Aizen’s 1991 TPB model to study help-seeking
intentions and success. Barriers they found included college students not seeing a value in
therapy, discomfort with emotions, lack of access, stigma, lack of knowledge, and
cultural barriers. Often college students felt the mental health issue will resolve on its
own (Downs & Eisenberg, 2012; M. Shea et al., 2019). These factors indicated a need to
educate college students and others about mental health and counseling and improve
awareness.
Summary and Conclusions
This literature review summarized research that addressed mental health concerns
in higher education. In a learning community, physical and mental health can be
important to reaching academic goals. Learning more about how mental health is
communicated and perceived can be helpful to improving health in a community. This is
important as mental health surveys are showing continuing issues in college students such
as depression and anxiety increasing (ACHA, 2019, Health Minds Network, 2021;
University of Minnesota, 2021).

The purpose of this study was to explore mental health culture at a college setting
for first year students and communication surrounding mental health issues. Culture
refers to the collective behaviors and customs on the college campus and more
specifically the behaviors and customs related to mental health. College students were
asked questions regarding their perceptions and experiences regarding anxiety and
depression, how these experiences impact student learning, and the impact of the college
cultures.
Chapter 3 contains the research method aspects. It describes the research design
and rationale, the role of the researcher and the methodology that will be used. The
participant selection process is described and the interview and artifact collection are
discussed including procedures for recruitment and participation. Chapter 3 also outlines
data collection and analysis and discusses resolutions for ethical and trust issues along
with the data quality related to transferability and dependability.
Chapter 3: Research Method
The current study explored mental health culture at a college setting for first-year
students. Several quantitative studies had been done investigating mental health that
showed increasing or stagnant rates of mental health diagnoses (ACHA, 2019; Healthy
Minds Network, 2023; University of Minnesota, 2021). My qualitative study explored
more how mental health is reflected in the higher education culture. The aim of this study
was to explore mental health culture by looking at communication methods and realities.
A basic qualitative design was used to understand the cultural norms for the
college campus regarding mental health in students, how they communicated with others,

and how they asked for help. Interviews and artifact collection with first-year college
students were used to answer the research questions. The rationale for this type of
research was to allow for an in-depth exploration of the culture of mental health on a
college campus and allow for comprehensive responses.
This chapter provides details on the research methodology including why and how
the research design was chosen. The population of study, sampling method, and rationale
are discussed. How the interview protocol was developed and tested are also reviewed.
Details are provided on how the data were gathered and analyzed, as well as the
procedures and process that ensured data integrity.
Research Design and Rationale
This study was designed to give further insight into the mental health culture of
traditional first-year students at a small community college. The focus was on first-year
students to study the culture of mental health during the initial transition that happens at
the beginning of the educational journey. There is an adjustment that happens when
students move from their local high school educational experience, live on campus, and
attend college classes (Bishop, 2023; Zeller & Mosier, 1993). The W-curve hypothesis
was initially proposed in 1963 by Gullahorn and Gullahorn as a model of how individuals
react to culture shock (see Figure 2). The W-curve hypothesis was later adapted to reflect
how first-year college students adapt to the change in culture (Bishop, 2023; Zeller &
Mosier, 1993). College students are confronted with a reality that may not always
correlate to their expectations (Bishop, 2023; Zeller & Mosier, 1993). College students
then may experience stressful emotions that may impact their adjustment, well-being, and

sense of belonging. Students may adjust but then have a setback when they go home for
the break between semesters. Eventually, they reach an equilibrium and better sense of
belonging (Zeller & Mosier, 1993).
Figure 2
W-Curve Hypothesis Model
Note. Adapted from Hoffenburger, et al. (1999).
The research questions for the current study addressed cultural issues that impact
college students’ mental health. The primary research question was the following: What
are the cultural norms regarding mental health in the individual and communication of
mental health issues? The secondary research questions were as follows:
•What were students’ understanding of perceptions and experiences of anxiety
in themselves and others at the college campus?
•What was their understanding of the relationship with anxiety and student
learning?

•What were students’ understanding of perceptions and experiences of
depression in themselves and others on the college campus?
•How did the campus culture support or hinder mental health?
•What were potential solutions for improving and maintaining student
wellbeing on campus?
Quantitative research existed on this topic and showed a significant percentage of
college students indicated they had experienced mental health issues such as depression
or anxiety with the percentage of students reporting these issues had increased over time
(ACHA, 2019; Health Minds Network, 2023; University of Minnesota, 2021). In the
current qualitative study, I used individual interviews and artifact collection with the goal
of learning more about this phenomenon. Using interviews rather than focus groups can
help eliminate issues of college students being impacted by other student comments. Peter
et al. (2021) found that when people feel differently than those in the group, it can cause
them not to address their mental health issues. Using individual interviews eliminated this
issue and allowed individuals to share information more freely without feeling influenced
or inhibited.
The research tradition that was used was a generic qualitative design. The
interviews and artifact collection provided information to gain a more detailed
understanding of how the community culture surrounding mental health impacts the
individual culture and vice versa. These findings may be helpful in determining more
impactful and effective interventions that may improve overall mental health and
decrease the number of college students having debilitating mental health issues.

Other research methodologies did not fit the research questions for the current
study. For example, the ethnographic design addresses the cultural aspects of a location
and specified population (Patton, 2014). The culture being looked in the current study
was specific to a college campus and residential first-year students rather than a particular
ethnicity. The primary phenomenon being researched was the cultural norms for
communication of mental health issues for first-year college students. As noted by Kahlke
(2014), using a generic qualitative design allows the research questions to be asked and a
matching approach to follow. Sometimes the correct approach is not an established
research method.
Credibility can be a concern when following a generic qualitative design. Caelli et
al. (2003) noted that providing clarity in the areas of theoretical positioning,
methodology, and method congruency establishes rigor, and an analytic perspective can
resolve any credibility issues. In the current study, the TPB was used to explore the
normative and behavioral beliefs behind mental health, the attitudes that resulted, and the
corresponding behaviors. The methodology included individual interviews to provide an
environment in which individuals could share responses without other participants
impacting their participation (see Peter et al., 2021). Methods focused on confidentiality,
for example using an unused conference room for interviews where college students had
complete privacy to share. Rigor was emphasized by recording and transcribing the
interviews and allowing for a follow-up visit where participants could review their
transcript and make corrections and additions. I also clarified assumptions surrounding
the theoretical framework in my data analysis.

Role of the Researcher
One of the roles of the researcher that was relevant to my study was the potential
power relationship. This would be a relationship in which either the interviewer or
participant had status that could influence or control the other person (see Rubin & Rubin,
2012). Not only are there ethical reasons for interviewing without undue pressure, but it
can provide inaccurate results (Rubin & Rubin, 2012). My study took place at the
institution where I taught in the small community where I live, so it was possible that I
would know the participants, or they would know me. Therefore, I excluded college
students with whom I had current relationships. The informed consent form provided
information about dropping out of the study at any time, and participants were given the
opportunity to withdraw from the study at any time.
Research should be valid and relevant, especially to the participating institution
(Rudestam & Newton, 2015). In the current study, regular updates were communicated
by email to student affairs, faculty, counseling, and wellness staff at the college. Any
questions that were raised were answered quickly by me. Because college students were
willing and able to give their time to improve the culture of mental health, I provided
them with copies of their transcripts, an interpretation and verification document, and a
$20 gift card. This served as a verification of the data collection and token of
appreciation.
The topic of mental health and cultural norms on a college campus could have
raised sensitive issues for the participants (Walden University, n.d.). I asked college
students about mental health and issues such as chronic depression, anxiety, and/or

suicide, which could have resulted in triggering certain thoughts. It was important for me
to think through as many possible sensitive issues that could have arisen, be prepared to
address these issues immediately, and provide participants with the support options
provided by the college community.
Methodology
Participant Selection Logic
Data were collected using semistructured interviews with approximately 12
firstyear students (18–19 years old) who attend school on campus. The goal of
interviewing at least 10 students was a rough estimate based on information from
Creswell and Creswell (2018). College students who volunteered to be interviewed came
from a variety of backgrounds, and information that was being gathered started to overlap
within the first five interviews. Interviews were concluded when the data collection was
not eliciting new insights or revealing new answers to the research questions (see
Creswell & Cresswell, 2018). The incoming 10-day census for fall of 2023 first-year
students was
346. The total number of undergraduates at the college where the research took place was
1,755 for the fall of 2023. First-year traditional students are encouraged to live on
campus, and participants who lived on campus were the population of the study.
I determined that using first-year college students would provide insightful
information because they are experiencing the campus culture with a fresh perspective.
They were able to describe their experiences as they transitioned into living in a new
environment. Because they were first-year students, their transition between high school

and college was recent and fresh in their minds. On-campus students were the population
of study because living and attending school on campus involves more experiences with
the inclusivity of the campus culture.
The entire first-year class was informed and recruited for the study. All college
students who participated lived on campus in the first-year dormitories, although they
lived on a variety of wings. Students who responded were primarily female and were
involved in a variety of activities. For example, students who were interviewed were
active in sports and clubs and came from various religious backgrounds and ethnicities.
More information on the participants is provided in Chapter 4.
Instrumentation
Learning more about why people feel or act in certain ways is an important part of
research (Rubin & Rubin, 2012). I used semistructured interviews and artifacts to gather
deep and rich data (see Rubin & Rubin, 2012). Being a skilled interviewer who
understands the importance of the process and the questions is necessary (Patton, 2014).
The interviews were semistructured with an established list of questions (see Appendix
F). Patton (2014) referred to this type of interview as a semistructured interview. My
interview questions were developed in a Walden course taken. Patton (2014) and Rubin
and Rubin (2012) were also used to provide guidance. The course was structured to allow
feedback from other students and the professor to improve the interview questions. The
questions were open-ended and allowed the respondents time to respond openly.
The interview guide was initially created in a doctoral course and was further
developed through test interviews and feedback from fellow students and instructors. The

interview guide was created to determine the cultural norms regarding campus mental
health and how they were communicated. My ability to test and adjust the questions over
time assisted in ensuring their validity and credibility. Rubin and Rubin (2012) noted
three approaches to determining interview questions, and a combination of these was used
in the current study. Because I had been teaching a class for several years that addressed
mental health, this provided a basis for developing interview questions.
Second, I used the literature review to provide information for the interview guide.
Finally, researching the questions as part of my coursework furthered the question
development. Patton (2014) stressed the importance of practicing to develop interview
skills. I was able to practice with older students at the college where the research was
eventually conducted.
The interview questions were tested using the two mock interviews that were done
to test the interview guide. The mock interviews were an assignment in a Walden course
that allowed for input from the professor and fellow students. The mock interviews were
conducted and shared in the course. This process indicated that the interview guide was
effective, although some improvements were made to answer the research questions more
effectively.
Codes were determined using the process outlined by Saldaña (2016), who
described coding as a heuristic process in which several cycles are used to discern the
meaning within the data. Data should be read through and/or listened to multiple times to
codify and categorize the data. Reflexive thematic analysis was then used to develop

themes from the data, which involved analyzing and interpretating patterns across the
data set (see Braun & Clarke, 2022). Possible first-level codes included the following:
•emotions
•confidence
•perceptions of high prevalence
•high stress
•multiple relationship possibilities
•transition problems
•counseling use issues
•mental health myths
•lack of understanding
•resources for talking
•gender notes
•people don’t want to share
•differences between mental and physical ailments
•know people with mental health issues
•isolating yourself
•difficulty multitasking, focus on illness
•don’t use campus services
•anxiety and depression
•community impact
•wellness

Procedures for Recruitment and Participation
Participants were purposefully sampled from all traditional first-year college
students who lived on campus. Although 12 participants were included in this study, this
number would have been increased if data saturation had not been reached. Data
saturation is an indication of when a researcher has reached an adequate sample size and
can discontinue data collection (Ravitch & Carl, 2016). Data saturation is reached when
no new information is coming in from the interviews, there is a repetition of answers, and
the research questions are sufficiently answered (Ravitch & Carl, 2016).
College students from the first-year class were targeted through flyers (Appendix
B) posted around campus and announcements from their year-long first-year seminar
class professors and teaching assistants. The first-year seminar class is often used to share
information and class announcements as all traditional students are enrolled and it’s an
effective way to communicate with the entire first-year class. The communication shared
was purely informational, and it was clear that student participation was purely voluntary
and would be in no way attached to the grading process. An email (Appendix D) was sent
out to these students requesting participants and included my contact information to
clarify any questions. Students who were interested in participating were asked to fill out
a form (Appendix C) that included a consent form and collected basic information that
allowed a diverse pool of participants to be selected. Participants were given a $20 Visa
gift card for participating at the second verification.

Procedures for Data Collection
College students were recruited and if they were interested in participating in the
study were asked to fill out a consent form (Appendix C) and a form that collected some
basic information that allowed a diverse pool of participants to be selected. Once students
agreed to participate in the study, they were provided with instructions and contacted to
ensure their understanding and answer any questions they had. The approach that was
used to collect data was two-fold. First, participants were instructed to collect artifacts.
Second, they participated in a semi-structured interview which began with preset
questions but allowed for variances (Patton, 2015; Rubin & Rubin, 2012). The study
participants were required to collect photo and audio artifacts that related to the research
questions (Appendix F), which they discussed in the interview. Examples of artifacts
were provided to study participants to stimulate thought and ease confusion about the
assignment (Appendix E). The collection of artifacts allowed participants to provide
information from visual, reflective, and thoughtful perspectives, which provided for
deeper meaning. They were able to contact me to ask clarifying questions while they were
collecting their artifacts.
Participants were interviewed inperson. A virtual option was possible, but the
participants all chose in person. This allowed me to read facial cues and provide deeper
meaning (Patton, 2015). Mental health stigmas are a sensitive issue (Wada et al., 2019),
and a face-to-face meeting allowed for a more empathetic, comfortable exchange. An
inperson interview also allowed for an easier encouragement of detail from the
interviewee (Rubin & Rubin, 2012).

At the beginning of the interview, the participant was reminded about the content
in the consent form and reminded that they had signed it. They were also asked if they
had any questions or concerns before beginning. I then described that the importance of
the information being collected, explained the reasons for the data collection, the benefits
of the study, and the purpose of the interview (Patton, 2015). The artifact submissions and
explanations were used in the interviews to clarify answers to the seopen-ended questions
depending on what a person answered, follow-up questions were asked that explored the
specifics of their personal experiences. Questions were also asked related to the artifacts
that were submitted.
Google Meet was used as the platform for recording and transcribing every
interview. The interviews were planned to last about 30 – 60 minutes. The iPhone Voice
Memos utility was also used as a backup recording of the meetings. Participants
completed a consent form and were provided with copies of the interview transcripts and
a summary interpretation of the transcript.
An ethical consideration was discerning any disclosure in the interview that would
indicate the interviewee is in danger, e.g., in the process of the interview indicated their
mental health is in crisis. Interviewees who were demonstrating a mental health crisis
would be referred to the college mental health clinic. This never occurred during the
research.
Data Analysis Plan
The interview transcripts were automatically transcribed using Google Meet. Each
interview was listened to, and discrepancies were corrected as Google Meet’s automatic

transcription process is not perfect. Each participant had one initial interview and a
follow-up interview. They also turned in six artifacts that were submitted as pictures in a
Google Document with explanations. The corrected interview files, including both the
initial and follow-up meetings, and the artifact documents were uploaded into NVIVO
14.
The coding process followed the process outlined by Saldaña (2016). The
interview data was coded using three different methods. In Vivo coding was used to
reflect the participants actual voices. It is used by beginning researchers and allowed for
coding of literal responses to more accurately capture participant meaning. Emotion
coding was used to reflect content related to feelings and emotions (Saldaña, 2016). As
the interviews were about mental health using emotion coding worked for analyzing and
noting perceptions around experiences of anxiety and depression. Values coding was also
used at it was a method to connect participants’ words to attitudes and beliefs which are
core components in the theory behind this research, the TPB (Ajzen, 2021). The first
round of coding In Vivo and emotion coding were used. The second round of coding,
values coding was used.
Issues of Trustworthiness
Trustworthiness means the study results were able to provide information that is
reliable and valid (Ravitch & Carl, 2016). Having a thoroughly prepared interview
process and guide, making and data storage methods, and generally, a well-thought-out
process can assist with ensuring trustworthiness (Ravitch & Carl, 2016). Researchers
need to pay attention to the details and remain vigilant throughout the entire process. One

process that was used was informed consent. College students who were interested in
participating were given the informed consent form, had to agree to participate, and then
demographic data was collected. After the initial interview, the transcript was listened to
and corrected as needed. Participants were then provided with the transcript along with a
summary of the interview. I then met with the participants briefly to make sure the
transcript reflected their thoughts. These tools allowed for a formal approval process of
the research participants’ thoughts and contributions (Ravitch & Carl, 2016).
Ravitch and Carl (2016) introduced relational ethics. They noted that accurate
qualitative research comes from the researcher developing a close relationship with the
participants. This close relationship needs to be developed, understanding ethical
considerations, and making sure participants are protected and established research
guidelines are followed. High quality research includes following rules to ensure
confidentiality and privacy are achieved and no harm comes to the participants (Rubin &
Rubin, 2012).
It was important in the reporting segment of the research to make sure privacy
concerns were attended to. For example, reports needed to be written so that they do not
reveal confidential sources (Rubin & Rubin, 2012). Allowing participants the ability to
look over the final report or any final notes of their interviews helped ensure validity and
allow participants input on how their words were portrayed (Ravitch & Carl, 2016).
Ethical and procedural concerns needed to be attended to at all points of the research.

Credibility
Credibility was enhanced by ensuring data is elaborate and thick. Interviewing of
study participants elicited complex and thorough responses (Morrow, 2005; Rubin &
Rubin, 2012). These data were utilized for a thoughtful and planned out purpose.
Proactive approaches and utilizing fellow researchers as well as advisors helped the
researcher think through the process to achieve the goal of good, credible data (Ravitch &
Carl, 2016). There are several effective techniques for credibility. For example, one way
is to create triangulation in the study (Shenton, 2004). Using a combination of resources
allowed for triangulation to double check the integrity of each source and provide more
breadth to the data (Patton, 2015). This meant structuring the study to allow for the results
to be collaborated from several different angles. Although all interview participants were
traditional college students in their first year of study, attempts were made to diversify the
group, which also is a method of triangulation. Participant backgrounds related to gender,
faith, culture, ethnicity, and activities (sports, music, art, clubs, etc.) were varied which
provided different perspectives.
Another way credibility was increased was by using the literature review as a tool
to reflect on results from past research in comparison to this study. When information can
be found from different types of sources in various locations, it lends credibility to it
(Creswell & Creswell, 2018). The sources included quantitative studies, interviews with
multiple students, and the collection of artifacts. Another method that was used was
member checks (Creswell & Cresswell, 2018). This involved meeting with the
interviewees after providing them with a finalized transcript and a document where I

provided my interpretation and summary of the interview. They were able to correct any
misconceptions or provide additional information if needed. I also asked additional
questions if any answers needed additional clarity.
Another way that assisted the research in being credible was learning the culture
and history of the people that are involved in the study (Shenton, 2004). Shenton noted
that understanding what exists prior to research can help with confirmation of the results,
improve accuracy which impacts credibility. This helped the researcher understand how
to develop a higher level of trust. It also helped the research team understand social
norms and decrease the possibility of any problems. Having a team of individuals helped
as well. If there are more people to double check methods and provide thoughts and
feedback it improves the overall study. This can draw attention to any problems with the
research and adjustments can be made to retain credibility (Shenton, 2004).
Building trust can be extremely important to collecting accurate and in-depth
information. Open and honest communication when talking and interviewing participants
builds high levels of trust (Rubin & Rubin, 2012). The researcher was respectful of the
participants and did not treat them condescendingly to build assurance. Also listening
completely and actively can also help build trust. This resulted in participants fully
participating.
Transferability
Transferability is the ability of a study to be applicable to a similar context while
still retaining unique attributes (Ravitch & Carl, 2016). Comprehensive descriptions were
utilized to provide a detailed narrative of how the interviews and artifacts were collected.

This allows for the ability to recreate similar research (Shenton, 2004). The researcher’s
experiences during the data collection were recorded and notes regarding the participants
and setting were taken. Connections were made between the interviewees reports and any
cultural or social contexts that exist on the college campus (Shenton, 2004). Details about
the participants general and specific situation the day of the interview were recorded. This
aided in showing transferability between this research and its application to other similar
settings. Connections were explored between existing data such as the
quantitative surveys done at other settings and with larger sample sizes to demonstrate
transferability.
Dependability
Collecting and recording data that is consistent between interviews and allows for
the collection process to be repeated is dependability. This consistency increased the
validity and ability for the research to be used more widely. Work can be done on each
component of the research to ensure this. For example, one important factor was taking
time to ensure the interview tool measures responses that answer the research questions
(Patton, 2015). Using an outside researcher to review the study and data collected was
another way to make sure the research was dependable. As a doctorate student, there is a
process for getting work approved and allows for several people to review the research
process and report. This also helped increase dependability.
Confirmability
One method that was used to assure objectivity is collecting data from a variety of
perspectives by including participants from a variety of backgrounds. The additional

perspectives added depth and detail to the data and findings (Patton, 2015). The various
perspectives were detailed and recorded to create an audit trail. Any work done on coding
was noted and recorded for reference. Another technique or strategy that was used is
reflexivity. The researcher needed to be aware of their own background and how they are
influenced within the research process. I kept a journal to detail any thoughts on the
research process as it happened with the intention of providing a narrative that minimized
reflexivity and provided information about influences my background had on the
research.
Ethical Procedures
Conducting research to provide valuable knowledge that can be utilized and
replicated by other researchers is a worthwhile goal. The ability for the research and
results to be used and to answer collective research questions relies on high quality,
trustworthiness, and credibility. The quality of a research study involves the scientist
being detailed and careful in planning and rolling out the research. For example, one key
milestone in a study is receiving institutional review board (IRB) approval. The IRB
makes sure benevolence criteria are met, meaning the research will do no harm to the
study participants (Ravitch & Carl, 2016). Harm can happen in many different and
unobvious ways, and the IRB takes a detailed look to ensure it is unlikely to occur. This
research was approved by both the IRB where the researcher is a student and where the
research took place.
Ethical concerns were addressed by utilizing a recruitment method that asked all
college students in the pool if they would like to participate. Students who volunteered

were provided with information about how the process would work and what the study
was for. Confidentiality was maintained by giving students code names that were used in
analysis and reporting. The key to these name codes will be shared only if necessary. The
data is shared on a secure Google drive.
IRB approval was obtained from Walden IRB with approval # 04-17-23-0662443
and the research site IRB approval #2048021-4. Recruitment was started after obtaining
IRB approval by providing the invitation to all first-year college students through their
first-year class communication channel. Information about general purpose of the study
and more specific reasons for the questions helped develop trust between the interviewer
and interviewee. It was important to be open and honest with the interviewee as it helped
increase motivation of the interviewee to provide more detail and be honest (Patton,
2015). At the end of the interview, the process for follow-up was shared with
respondents.
Summary
The interviews were conducted at a local college with a carefully laid out plan.
College students were recruited from the first-year traditional class and interviewed.
Opportunities to discuss and gather personal beliefs and intentions through interviews
were used to create a final dissertation report that provided insight on the culture of
mental health at the study site. The interviews were used to make recommendations for
possible interventions to consider that can improve the environment, both health wise and
academically. Responses from the interviews were coded using descriptive coding and

grouping responses into themes. Several methods such as triangulation and utilizing other
researchers to review the process and data were used to ensure data trustworthiness.
Chapter 4: Results
The purpose of this study was to explore mental health culture for first-year
students at a small private college in the Midwest. A qualitative study was conducted
using interviews to allow for in-depth answers and exploration of the mental health
culture of first-year college students in an on-campus college setting. Interviews and
artifact collection were used to determine the cultural norms for students entering the
college community and how these norms were communicated. The primary research
question was the following: What are the cultural norms regarding mental health in the
individual and communication of mental health issues? The secondary research questions
were as follows:
•What were students’ perceptions and experiences of anxiety in themselves and
others at the college campus?
•What was their relationship with anxiety and student learning?
•What were students’ perceptions and experiences of depression in themselves
and others on the college campus?
•How did the campus culture support or hinder mental health?
•What were potential solutions for improving and maintaining student
wellbeing on campus?
In Chapter 4, the setting is described, demographics presented, and data collection
detailed. The participants are defined, the data collection process is outlined, and any

variations or unusual circumstances are noted. Evidence of trustworthiness is then
described. The results are presented and themes are addressed with examples from the
data to support them. Any nonconforming data or data discrepancies are noted.
Setting
The setting for this study was a small, private college campus in the Midwest.
Interviews were conducted on campus in person in a private conference room. The
interviews were recorded and transcribed using Google Meet and the iPhone Voice
Memos application. Artifacts were also collected from the participants and uploaded into
a Google Drive folder shared by the participant and me.
Demographics
The participants were 18 or 19 years old and were residential, first-year students at
the college where the research was done. Participants were from various cities in the
Midwest and from rural and metropolitan areas. The college is grounded in a Catholic
tradition, and students are asked to identify their faith tradition. One student identified as
agnostic, four as Christian, one as previously Episcopalian, and six as Catholic. Ten
students identified as female, one as male, and one as nonbinary. Nine students identified
as White, one as Latino and White, and one as Mexican. The students all participated in a
variety of activities and hobbies.
Data Collection
College students were recruited using flyers (see Appendix B). The flyers were
posted by a student teaching assistant and me on bulletin boards throughout the college.
The study was also announced or posted in targeted first-year online course sites, classes,

and meetings. First-year class and advisement programs for all first-year students were
used as the primary vehicle to recruit students. The flyer was distributed to faculty and
teaching assistants to share within in first-year classes. Residential advisors also emailed
and/or posted the flyer for first-year students who lived on their units.
College students who saw the flyer could click on a link or scan a QR code, which
brought them to the consent form. If they consented to participate, they were asked for
demographic data. The initial process to sign up for the research took less than 2 minutes
to complete, which included both the consent form and demographic information
collection. The consent form was a Google Form that was managed in a Google Sheet. I
was the owner of the Google Form and Sheet, so I had control of the data within it and
checked regularly for new submissions. Once participants had completed the consent
form and participant information form, I communicated with them through email (see
Appendix D). I gave them my phone number if they preferred texting or calling rather
than using email. The artifact collection instructions (see Appendix E) were provided,
along with a link to a folder shared by the participant and me. Participants were instructed
to contact me if they had any questions. Participants were asked to set up an interview
time with me on a bookable Google appointment schedule. Once data collection was
completed, the form was closed to responses.
During the Fall 2023 semester, 14 college students responded to the survey and
completed the consent form. Of these, six submitted artifacts, were interviewed, and
completed the research process. One of the six participants who was interviewed did not
meet the research criteria because they were a sophomore transfer student and not a

firstyear student, so the data from that participant were excluded. One of the 14
participants submitted an artifact but never was interviewed. One participant scheduled
their interview for spring semester. Five of the 14 participants signed up and submitted
the consent form but did not proceed further with the research. Participants did not give
any reasons for dropping out, but it is possible that as they progressed into fall semester
and had a heavier academic load, they were unable to find the time to participate.
In January 2024, an additional eight participants responded to the survey and
completed the consent form. Of the additional eight participants, six collected artifacts
and completed the interviews. Two of the participants who completed the consent form in
January did not respond to further emails and were not interviewed.
Participants were asked to collect six artifacts (see Appendix E) over the course of
2 weeks. This was estimated to take about 30 minutes to collect all six artifacts. The
artifacts were items, such as a picture or words, that represented or gave meaning to a
concept. For example, participants were asked to provide an artifact of an emotion they
were feeling. These artifacts allowed participants to communicate using visual, auditory,
or kinesthetic examples of their thoughts related to mental health. The artifacts were
collected by the participant and submitted to a Google folder shared by me and the
participant. The participant wrote why they collected the artifact and discussed it in the
in-person interview.
Participants were given a choice of meeting virtually or in person, and all of them
chose to meet in person. The remote nature of the conference room ensured privacy and
confidentiality, but it was still easily accessible for on-campus college students. The

interviews lasted 33 to 61 minutes and were recorded. The average length of the
interviews was 49 minutes. A transcript of the interview was created from the recording
with Google Meet. I listened to the transcripts and corrected them as needed. Once this
process was completed, the participant was given access to the final transcribed interview
for review. I met with the participants so they could provide any additions or corrections.
These follow-up meetings took 4–30 minutes with an average of 12 minutes per meeting.
Data Analysis
The collected data were organized and stored in a Google file where they could be
shared with participants and my committee chair. The data included recordings of the
interviews, scrubbed transcripts, notes, artifact files, and interpretation and verification
documents. Data were stored in a Google folder to allow the participants to have access
for verification purposes. NVivo 14 was used for coding and analysis.
The interview transcripts were transcribed using Google Meet. Each interview
was listened to, and discrepancies were corrected because Google Meet’s automatic
transcription process was not perfect. Each participant had one initial interview and a
follow-up interview to clarify any discrepancies or make any additions. An interpretation
and verification document that summarized key points was provided to participants along
with the full transcript for review before the follow-up meeting. Participants also turned
in six artifacts that were submitted as pictures in a Google Document with explanations.
The corrected interview files, including the initial and follow-up meetings, and the
artifact documents were uploaded into NVivo 14.

The interviews and artifact documents were uploaded to NVivo 14 and were
reviewed for key words or phrases. The key words or phrases were assigned a code. The
coding process followed the process outlined by Saldaña (2016). The interview data were
coded using in vivo coding to reflect the participants’ voices. In vivo coding is used by
beginning researchers and allows for coding of responses to capture participants’ meaning
(Saldaña, 2016). The codes were then categorized by primary comment topic, and the
main themes were drawn out of those categories.
Evidence of Trustworthiness
Trustworthiness means the study results provide information that is dependable,
legitimate, and reasonable (Ravitch & Carl, 2016). The study results are reliable and valid
as several steps were taken to allow for this. The strategies for ensuring trustworthiness
are credibility, transferability, dependability, and confirmability. The interview guide was
prepared and used for each participant. Participants’ verbatim words were recorded and
transcribed by Google Meet, and then I listened to each interview and corrected any
errors with the automatic transcription. Although the script was used as a basis for the
interviews, I was able to go off script as needed. All of the questions were asked even if
the interview veered off script. The data were stored in files on my hard drive and also
within my Google Drive. Each participant was given access to the transcript and a
summary document that interpreted the interview. The participants were able to review
their transcript and make any corrections or additions.

Credibility
Credibility refers to the ability of the researcher to deal with inconsistencies or
difficulties in explaining the data and provide clarity in a meaningful way (Ravitch &
Carl, 2016). The strategies used for credibility in the current study involved a process that
accurately captured the interviews. Google Meet was used to record and transcribe the
interviews. This allowed me to listen to the participants and provide transcripts that were
reviewed and corrected following the interview. A follow-up interview was conducted in
which participants had the opportunity to review the transcript and make any corrections.
At the follow-up interview, I also asked any questions I had for clarification of comments
from the initial interview.
Triangulation was one of the methods used to ensure credibility. Triangulation
involves verifying and ensuring accuracy by checking the data with other sources and
understanding any inconsistencies (Shenton, 2004). Throughout the research process, I
used other resources that addressed mental health in the college community. For example,
I examined large-scale quantitative resources that summarized research done at colleges
across the United States (Health Minds Network, 2023; University of Minnesota, 2021)
as one check of the integrity of the data. When various sources are used, this provides
breadth to the data (Patton, 2014). A few preliminary demographic questions were asked
after the consent form was approved. The results from these questions showed that the
college students being interviewed were involved in many different activities, came from
a variety of hometowns (rural and urban), had many different majors, and had various
faith backgrounds.

Another method that was used to increase credibility was member checks (see
Creswell & Cresswell, 2018). The member checks were meetings that were less than 30
minutes and set up after each initial interview. After each interview, I listened to the
recording and made corrections to the transcript. I then created a summary of the
interview with my interpretation of the content and verified that with each participant. I
also asked for clarification of anything I felt I needed to understand better to eliminate
misunderstandings. Participants were able to add any information they felt they missed
sharing in the initial interview. A multiple-step process that allowed participants to see
and verify what they had said created trust between me and the participants.
Transferability
Transferability is the ability of a study to retain some properties of similar
research but have unique components as well (Ravitch & Carl, 2016). Components of the
research are explained in detail to allow for the ability to create similar studies (Shenton,
2004). My experiences during the data collection were recorded, and notes regarding the
participants and setting were taken. One issue that came up was the difficulty in getting
participants to volunteer. Participants were willing to volunteer in the first few weeks of
the semester but then got busy and were not able to participate. I was able to collect five
usable interviews during the fall semester and then revised my methods through the IRB
to add other recruitment techniques. I put up more flyers and went to meetings to
encourage residential advisor and staff, who both had access to first-year college students,
to share my study flyer. I also was able to go to one class.

Dependability
Dependable data are collected by having a well-thought-out collection process and
following the same process for each interview (Ravitch & Carl, 2016). Throughout the
data collection process in the current study, the research questions were kept on hand to
make sure the interview questions were providing answers to the research questions (see
Patton, 2014). The interviews were done in a private conference room. When the first
conference room was no longer available, a similarly private space was found. Allowing
for interviews to be conducted in person in a private and accessible setting added to the
dependability of the data. The focus was on the questions and sharing information
without distractions from other individuals or people able to overhear responses.
Another component that ensured dependability was to have a team review the
process, ask questions, and suggest improvements. My chair and committee member were
able to do this, which added to the quality of the research process. Having more than one
voice in the process improved the output.
When data show consistency over time, they are considered stable (Ravitch &
Carl, 2016). This was demonstrated throughout the current study. One limitation of the
study was that it was initially meant to be completed during the fall semester. Because
there were not enough participants in the first semester, there needed to be a second call
for participants during the second semester. The data may have varied from one semester
to the next, but the variations did not appear to be substantial.

Confirmability
As I bring my unique perspective to the study, confirmability means the study can
be corroborated beyond one perspective. Although one individual’s perspective can add
depth and valuable information to the results (Patton, 2015), breadth can be beneficial.
Detailed notes and a collaborative process allows for the process to be checked and
double-checked as needed and adjusted appropriately. Detailed notes on the interviews,
summaries, coding, categorization, and theme creation allows for others to check my
work and assure that it can be collaborated. Another piece that helped me reflect on the
perspective I was bringing to the research was keeping a journal where I could note
thoughts regarding what participants shared, how I coded them, and my process thoughts
along the way.
Results
The results follow and address the primary research question directly and the
secondary research question through the presentation of various comment themes. I
believe the participants were forthcoming with honesty and noted that this was research
and they wanted to be transparent. Quotes from the interviews and the artifact
submissions were utilized to support the themes. All participants were first year students
and had attended the college where the interviews took place both semesters, except for
one participant who transferred in for spring semester from a nearby college. This
participant’s contributions may be impacted by attending a different school for a
semester.

Definitions and Understanding of Mental Health
The themes that follow are better understood when placed into context by the
meaning of mental health, illness, anxiety and depression in the words and pictures of the
participants. Some participants defined it by what they experienced themselves or
witnessed in others, others defined it based on their general understanding. A list of the
definitions and feelings associated or thought to be associated with mental health,
anxiety, and depression are included in Appendix I. The participant definitions were
provided as the many different descriptions illustrate how difficult it was for participants
to broadly define these terms for everybody, it can be easier to define them from an
individual perspective. As participant L stated, “Mental health, it’s different for everyone.
It’s one of those things that you can’t categorize for each person. Someone can tell you
that they have anxiety, but that doesn’t mean your anxiety is the same as their anxiety.”
Defining it personally can also be difficult as when you are having poor mental health it
can be hard to mentally conceptualize what is going on. “I see mental health as basically a
just like a struggle” (Participant J). It is also directly connected to your physical health
which adds a complexity. Participant L shared an artifact picture or a cell phone battery
flashing at empty (Figure 3). They noted, if you don’t have your phone charged you can’t
connect with other people...similar to my brain if I’m not charged. I don’t want to connect
to people in person. I don’t want to be around people if I’m low battery wise. …My
mental health personally runs on what feels like a battery system. If I don’t give myself
enough of a break/charge, I’ll only get worse/more low.

Figure 3
Participant L Artifact: Low Battery
Participants often used the word “stress” or “stressed” to describe their anxiety.
Participant B used the word “spiraling” for anxiety as they found “it feels utterly out of
control.” Participant K noted that it felt as though “there is a little gremlin in your brain,
that just is like going a million miles an hour bouncing off the walls and never giving you
a break.” Participant J described their anxiety as follows:
like a hamster on a wheel. So, you feel good, so your hamster is asleep on the
wheel, but as you get more anxious, if you feel more worked up then he’ll start
running and it’s like we need to get the hamster back off the wheel.
Participant J also noted it’s like there are “two brains in their head. One is the
normal brain that I can make focus and I’m thinking about work or dinner...and then my
other brain is all the homework and school and the hamster on the wheel again.” Many of
the participants commented that anxiety and depression are linked. “Some people that get
so anxious about life that it might cause them to be depressed” (Participant I). Other
comments described depression as a much more withdrawn state, “I was in such a dark

space and I was using up all my energy to stay alive” (Participant E). There were also
comments that reiterated the inability to control depression without help, As noted by
Participant A,
I’d be surrounded by people that I love and there would...be a little bit of
loneliness and sadness in there...and so it would be hard to fully enjoy things...it’s
like everybody’s so happy, but then the person’s like really off to the side and
very in pain.
Participant E described depression like a tornado spiral. Participant K like a “weighted
blanket, but not in a good way. More like a heavy sheet that just kind of lays on you and
compresses you and shuts you off from the world.” Mental health and associated
diagnoses can be found on a continuum, one side is perfect mental health and on the other
side is serious and/or persistent mental illness. Participant B noted the difficulty in
understanding where one is at on that continuum, “I wasn’t sure at what point sadness
actually turned into depression. How long did it have to go for?” This can be very
individual.
Theme 1: Community Culture
The theme of a multifaceted and resource rich community that supported and
addressed student mental health came out strongly in the interviews. Participants
described the community at the college as “exceptional” and that it provided many
resources for students if they are needed or if they chose to use them. Participant E
defined community as “the community to me is just like people, I love, I’m surrounded

by, and support me.” Various aspects of community were used and that varied for
participants.
Participants noted that their primary circle usually included their friends,
roommates, and/or teammates if they were involved in formal activity. Participant J
noted, “even without wanting to try to build a community, you just already have them
around you.” Generally, the individuals in their community were the first people
participants would go to if they had a mental health concern. Participant B provided an
artifact that was a picture of a sports video game and noted the game demonstrated the
importance of community in the meaning of mental health for them:
Community: My friend and I love to play this video game together. He always
says how much he enjoys that time with me. Playing video games is vital for our
mental health and maintaining a close network of friends to go to with your
problems.
Several participants felt a strong sense of independence and would first work on
solving the problem by themselves. As Participant C noted,
I am definitely closer to some people than others. But I know if I was struggling
with something and one of them walked by, I know they would help me that kind
of thing but with deeper stuff I would probably go to… I made two close friends
on that trip (pre-fall semester activity) … So, I’d go to them with any deeper
problems that I have but I tend to refuse help, I like being independent. So, I
would try to figure it out myself first.

Participants that had a roommate that they could immediately share concerns with
as they happened, really appreciated having that ability. The emotional energy of
roommates or friend groups were helpful or stressful. For example, Participant L noted
that sometimes she didn’t want to go to the gym, but her roommate made her, “I feel
obligated to get up and do it for her...my body doesn’t want to get up but in my brain I’m
like, I will feel so much better.”
Residential advisors (RA’s) were seen by some participants as supportive and
someone that could be counted on. However, participants noted that some RA’s did not
reach out or come across as approachable. Participant J moved from one unit to another
between semesters and describes the difference between RA’s,
That RA was really distant she never really talked to us. I don’t think she even
knew our names. So, when I switched this new RA, she’s super nice, always
sends out newsletters and emails and tries to talk to us in the hall. So, I already
feel like I already have another person to go to if I need something so that’s really
nice.
Participant B noted the importance of, “just hiring really good RAs that are
extremely involved and constantly checking and our floor RA is amazing and they are
just super…they’re always checking in on us and making sure that we are feeling okay.”
In contrast, Participant E said, “I don’t really know my RAs.” Participant L mentioned
that their RA’s put a diagram of the W-curve (see Figure 2) on their bulletin board and
noted that it was helpful to have repeated information from their RA’s that they had seen
during welcome week. It made the participant feel as though the RAs understood what

they were going through and reminded them that their RA went through it as a first-year
student.
Participants said that the W-curve was introduced during welcome week by the
Dean of Students. They felt the Dean’s welcome week presentation was memorable and
helpful and that the W-curve was a helpful concept for students to reflect on as they
adjusted to college. Two-thirds of participants noted that the Dean was someone they felt
they could go to with any mental health concerns and two participants had positive
interactions with her when they needed help. Participant B remarked, “She radiates
positivity, so I feel like you couldn’t talk to her very long without feeling better.”
Participant F noted a problem their roommate was having that was brought to the Dean’s
attention and when she came back from meeting with the Dean she said,
I’m just so relieved like she listens to me. She understood me. She validated how
I was feeling. I thought she was gonna try and just immediately provide solutions,
but she listened to me and heard my side of the story.
Participants mentioned the Dean of Students unsolicited and appeared to feel she
was a community presence that was there to support them. The final group that was
mentioned repeatedly by participants as part of the supportive community were
professors. Most comments were positive such as Participant C’s, “it seems like the
teachers...want you to be at your best too.” Participants noted that professors not only
pointed you in the right direction if you needed something, but they were willing to have
a conversation and they listened to college students as well. Participants point out that
professors have office hours and many give mental health days. A few participants noted

they would never use the mental health days. Participant K stated, “I would never take a
mental health day, it’s just ingrained into my brain...you go to class, you show up every
day. You push through, you don’t take a day for yourself.” Professors appear to be
providing options to support mental health even if college students are not ready to utilize
these options.
Participants rated the campus options for mental health support at 5.6 on a scale of
1 to 7 with 1 being the worst and 7 being the best. Participant K rated the mental health
support on campus at a 2 and shared the story of calling counseling during Fall semester
and being told they were busy and to call back. Participant F rated it a 5 and noted
“there’s definitely stuff for people that need it but like I was saying with my roommate, it
was really hard to get a counseling appointment.” Overall, participants had higher
rankings for activities and community members that supported their mental health.
According to Participant A and an artifact they shared (see Figure 4), there are some ups
and downs to finding your place in the campus community:
This song, The Fun in Life, helps me remember that life is a roller coaster and that
it isn’t always perfect. You have people around you that you can depend on. One
of the hardest parts about living on campus for people that I’ve talked to is finding
routine, and finding who your friends are.
Figure 4
Participant A Artifact: Fun in Life (Elton Castee, 2019)

Theme 2: Mental Health Stigma
Although there were many community support systems, there was a component of
mental health that is still hidden on campus. In the health care continuum model (Chen et
al., 2020) participant’s comments indicated a stigma if an individual is trying to
communicate that they are having mental health struggles. There are only certain aspects
of mental health concerns that can be shared or communicated openly. Participant I noted,
“society kind of makes it hard to come out with what you feel.” Many of the participants
talked about how they feel there are resources and options on campus for talking about
mental health, but they have experienced or seen situations where mental illness is often
not acceptable to share. Participant H shared the story of her roommate crying and she
called it a breakdown. They talked briefly about the issue, her roommate dried her tears,
and they both went off to class as if nothing had happened. Participant A noted that they
could talk openly with their professor which they found helpful, but they couldn’t tell
them everything because they would be mandated to report it. Participant L noted that
“sometimes I find I tend that I keep a little bit of the truth away when I’m talking to loved
ones” although they may tell them more when they are feeling better in a day or two.

There were several reasons for this hesitation to openly share, including a societal
pressure to be happy, a need to not be different, and a discomfort with feelings that are
difficult to address. Participant I noted that there is a public persona of happiness that
feels like a fake happiness.
Society kind of makes it hard to come out with what you feel. I don’t know.
You’ve probably heard multiple people say this, but social media just shows the
positive side of everything and I see all my friends back home and they’re posting
all the happy moments in their life. And I forget that other people struggle with
things as well.
Another participant struggled to accept help or studying and test accommodations as they
did not want to be different from others. Participant B described a situation where “a
friend may be looking at his phone and going ‘I have just been feeling really depressed
lately’ and somebody would just be making a joke about it.” They noted it can be hard to
be taken seriously about mental health issues with friends. Situations were also described
where people aren’t able to acknowledge their mental health problems, so their loved
ones feel helpless as they sit and watch problems fester.
Theme 3: Toolbox
The toolbox are items or methods the participants use to manage their mental
health. Contents of the toolbox can be a wide variety of things like all kinds of physical
exercise, music, breathing techniques, art, visualization practices, mindfulness, etc. Each
person’s toolbox is unique to them. Specific items mentioned by participants during the
interviews can be found in Appendix J. Participant E noted,

Yes, I’ve definitely gone through a roller coaster of figuring things out. It’s just
like if one thing doesn’t work for you, then try something new. If that doesn’t
work for you, try something completely different, and if it sort of works, give it
another try another day. Maybe it’ll work, maybe it doesn’t.
Participants noted that practicing and using their tools when they were mentally
healthy made the tools easier to use when they were struggling with mental health issues
as they are more habitual versus needing more thought to use. Using the toolbox can be
helpful, but sometimes when struggling with mental health, the toolbox can be difficult to
put into practice. As Participant K noted when explaining their ranking for how they care
for their mental health,
It’s hard work. It’s hard to deal with it and actually use the tools that your
taught…. I would say that I have the toolbox and I carry it around with me
everywhere. Do I open it when I need it. No, finally it’s like if I was in my
kitchen, I had all the ingredients to cook a meal and I just didn’t cook it. That’s
kind of what my four is.
Participants were asked, on a scale of 1 to 7, 1 being bad and 7 being good, to rate how
they felt they take care of their mental health. The average of the 12 participants was 4.9
with all participants choosing a 4,5, or 6. Many commented that their ranking varied and
that they could do better at caring for themselves. Community support such as friends or
roommates using your tools with you can help.
Changes in one’s life can make it difficult to use the toolbox. As Participant K put
it, “And then the first semester I was like, hey guys. I feel like I left my toolbox at home.

Like guys, I’m so lost. I think I threw the key in Lake XXX. I might need a new toolbox.”
As people transition into new roles and new locations, they need to assess their toolbox,
determine what tools will still work, and decide where they need to make changes. Just as
new homeowners are often given a toolbox as a housewarming gift, a new virtual health
toolbox may need to be developed when moving on campus and into the next phase of an
individual’s life.
Theme 4: Counseling Services
Participants spoke about having successfully used mental health therapy in the
past and spoke highly of both primary care physicians and therapists who had helped
them and were still available if needed, even if they had moved away for college.
Participants also discussed the on-campus counseling services, which were noted as high
quality for example, Participant B noted “the counseling on campus I’ve heard is really
good.” Participants mentioned that access to the on-campus counseling services was
challenging. Participant L noted that “One of my good friends on campus...he needed to
go to therapy and it took him weeks to get in.” Communication with on-campus
counseling services also left some participants frustrated. Participant D noted that they
“did actually reach out to them but they didn’t respond.” They noted “I like emailed and
didn’t hear anything back. I’m like, it’s a sign that I don’t need to go.” Participant K
noted that this was their only resource for counseling and they were told the service was
booked out for two months and to try again in the spring semester.

No, they were like we’ll let you know when something opens up. So I was like
well… and then it’s always like “If you need severe mental health help, please
call the hotline.” No, I need therapy, please. I just kind of felt like, pushed aside a
little.
Participant F noted “I don’t even really know where the counseling office is. I felt like
they should have been okay, this where it is because sometimes even that gives you
anxiety...I’m going to walk around all lost...I felt someone once said, if you get someone
to a space once, they’re more likely to come back.”
Another issue with communication regarding counseling services was that
everyone assumes it was someone else that needs it and not a personal need. Participant H
noted that during covid their high school put out a lot of emails regarding counseling
services and the importance of mental health,
I feel like I didn’t think I needed it. A lot of people don’t think they need it. Like
my high school put out a lot of emails like counseling services will resume and
the importance of mental health, but I think a lot of people thought that it wasn’t
for them.
When asked how it should have been framed, the Participant H noted “more people
should have used them maybe if it was framed like a check-in... people seem to not want
it be like in therapy or a mental health thing.”
Theme 5: Mental Health and Student Learning
Another theme that emerged from the data was that academics and student
learning appear to be synonymous with anxiety and stress. Participant L noted, “It just
gets kind of bad during the school year when I have a lot of workload, but during the
summer I’m pretty much fine.” Participants appeared to be actively planning when and
how to study but this didn’t seem to prevent procrastination and test anxiety. Participant
D shared a photo of their calculus homework as an artifact and noted they were feeling
stress. Participant D went on to say,
I had a Calc exam later that day that I didn’t prepare enough for and I was stressed
about it and having a difficult time understanding the material. I was studying for
the exam and wondering how on earth I’d get a good grade on it.
Participant K shared a picture of their chemistry notebook in an artifact (see
Figure 5) with the comment, “Today I was feeling extremely anxious and defeated. I am
struggling to grasp the concepts we are learning about in chemistry. This is a photo of my
chemistry notebook where I take lecture notes.”
Figure 5
Participant K Artifact: Chemistry Notebook

Even when college students receive good grades if they aren’t perfect, they
wonder if they could have done better. As Participant C put it, “It was still a good grade,
it was above the class average...but I could have done better.” Even though they are in
college where they should be learning more, it causes anxiety to not know. Participant K
noted, “I struggle a lot with not being perfect and not knowing everything.” The anxiety
can spread from student to student as well. Participant E discussed the nervous energy
that can arise, “I know when she’s anxious cuz then I feel anxious. It’s kind of like we’re
back and forth popcorning at each other...the tension is in the air; you can feel the
energy.” The spreading of nervous energy or stress was particularly noted during finals
week or around common tests or big assignments. Participant D noted with their
chemistry book picture artifact the following.
My teacher was talking about that (an assessment) was due on Friday evening at 8
o’clock but her was like, if you are really struggling with it, don’t just stress about
and let it ruin your entire week. You can take some time; you can try and figure it
out. You can contact me and we can work it out. You’re more important that the
test.
Even with a professor communicating clearly, not to stress and there is flexibility, it
doesn’t appear to be eliminating the stress of academic pressure.
Summary
This chapter summarized the results of a qualitative study utilizing semistructured
interviews and artifact collection to better understand the mental health culture that exists
for first-year students at a private religious college in the Midwest. Participants were able

to define and illustrate the meaning of mental health, illness, anxiety, and depression. The
community culture was found to be supportive and participants found connections with a
variety of people including friends and roommates, RA’s, campus staff, and professors.
Findings showed that although the campus was a mostly open and supportive community
when it comes to mental health, there were still some things that are struggles or stressful
for students. There was still a level of mental health that was not openly shared.
Academics maintain an element of pressure even with professors that are making
attempts to focus on learning and provide options to lessen the stress on students.
Counseling services was positively regarded for therapy services, but participants
struggled to get appointments. Participants overwhelmingly had tools that they used to
take care of their own health. Chapter 5 provides an interpretation of the findings,
implications, limitations, and recommendations for future studies.
Chapter 5: Discussion, Conclusions, and Recommendations
The purpose of this study was to explore cultural norms and how mental health is
communicated, perceived, and experienced at a private religious college in the Midwest
by first-year students who live on campus. The study was conducted using a social
constructivist and constructionist approach to explore students’ reality and how mental
health was communicated in the community. Research conducted on mental health across
the United States at colleges showed increasing and significant rates of anxiety and
depression in this population (Healthy Minds Network, 2023).
Interviews with participants provided vivid descriptions and definitions for mental
health topics. Mental health definitions in the words of participants set the state for the

following themes. Theme 1, community culture, illustrated an overall openness to general
mental health and a multifaceted network of individuals forming connections and
providing support. Even with this supportive community, a continued stigma regarding
more serious or mental health issues remained and was illustrated in the second theme,
mental health stigma. In the third theme, toolbox, participants shared the tools they used
to address their mental health. Participants had a wealth of tools to prevent and take care
of mental health that they were fairly effective at using. The fourth theme focused on
counseling services. Participants used counseling but struggled with making
appointments in the on-campus counseling service. Theme 5 illustrated the connection
between mental health and student learning. The participants struggled with elevated
levels of stress from achievement anxiety and studying, but comments from participants
showed improvements had been made.
Chapter 5 provides an interpretation of the findings that connects the findings to
the literature review in Chapter 2 and discusses how the current study confirms and
extends the reviewed literature. Limitations of the study are also presented, and
recommendations for future research are discussed. Finally, positive social change
implications from a practical, theoretical, and methodological perspective are described.
Interpretation of the Findings
The Chapter 2 literature review revealed three main points that were illustrated
broadly by the findings from the interviews. First, a stigma still exists with mental health.
This was emphasized in the interview data collection as participants noted a level of
mental health still not easily shared. The research knowledge around mental health was

limited, and there were many gaps. This point was also illuminated in the interviews,
especially with the descriptive definitions given for mental health issues. The second
point mentioned in the literature review was that maintaining health (both mental and
physical) is multidimensional and can be maintained more effectively when looked at it
from the preventive perspective. Focusing on aspects of health before acrisis can be
helpful in many ways. Third, mental health is often viewed from the mental illness
perspective. Switching this perspective to one of mental wellness and understanding that
all individuals have mental health was noted in the literature review. Current participants
were mixed in their comments about their ability to communicate this, although they
seemed to understand this. The difficulty in communicating could be caused by historical
language choices, which could be addressed in another study.
The findings from the interviews complemented much of what was found in the
literature review. Many of the current findings elaborated on or provided more detail to
other study findings. The first topic shared in results presented participants’ definitions of
mental health, anxiety, and depression. The definitions and descriptions given by
participants were much more descriptive of how their mental health can impact their
studying and learning compared to quantitative research and the definitions included in
Chapter 2.
The theoretical foundation for this research was the TPB, which included
constructs of behavioral, normative, and control beliefs and explores how they impact
behavioral attitudes, subjective norms, and perceived behavioral control. These constructs
are also used to explore the difference between intention and behavior (Ajzen, 2021).

Behavioral beliefs are whether it is subjectively believed that an action will produce a
result (Ajzen, 2021). Normative beliefs are the behaviors college students engage in
because they believe those are the acceptable behaviors by other students or members of
the college community (Ajzen, 2021). Control beliefs are related to what students feel is
within their control related to mental health and the care of their mental health (Ajzen,
2021).
Theme 1, community culture, related primarily to the behavioral and normative
beliefs constructs. The actions by the community members define what is culturally
acceptable. The culture of a college community can be like an invisible force that impacts
student behaviors in a common way that positively influences their physical and mental
health (Xu, 2020). The community culture can cultivate the development of other factors
such as belonging, social connections, and habit development (Xu, 2020), which aligns
with the current themes. One key finding from my study was that although the
community was largely supportive of college students’ mental health needs and the
attitude toward mental health was positive, this viewpoint did not always lead to openness
when it came to mental health.
This finding was illustrated in the first theme of community culture. Although the
individuals in the community generally talked about mental health freely, they did not
always feel comfortable to share personal issues or problems they were having. For
example, a participant could believe that by practicing self-care and going to a counselor
they were taking care of their mental health. Normative beliefs are what first-year college
students see as socially acceptable. For example, findings from my study showed that

participants did not see other students taking effective care of their mental health.
Participants heard staff, professors, and residential advisors saying therapy is a good idea,
but had not heard of anyone using it. Another barrier was reported regarding when
students were in a mental health crisis. During a crisis, they were not in a cognitive state
to seek help and take the actions that would improve their health. A student may have
intended to use therapy when they were feeling healthy, but that intention was clouded by
negative thoughts.
Theme 2, mental health stigma, demonstrated that although there was an openness
to sharing some mental health issues, there was a stigma to sharing too much. This theme
relates to the normative belief construct in the TPB (Ajzen, 2021). Stigma was defined as
an unfair negative belief about a trait (Kuhlman et al., 2019). This is confirmed in the
literature of Link and Phelan (2006) who defined stigma as how humans are stereotyped
by how each person sees differences with people around them. One difficulty with mental
health is the inability to see the changes. The existence of a stigma was found in the
current interviews and confirms the results noted in Chapter 4. Findings from my study
confirm Link and Phelan’s (2006) findings that stigma can lead to a lack of available
resources and counseling availability.
Current participants who had not attempted to use counseling did not feel they
needed therapy and did not want to take services away from others whom they thought
needed it more. This is similar to research by Eisenberg et al. (2012) who found that
college students who did not use therapy did not feel their problem was serious enough or
they did not have time. Students’ reasons for not going to a therapist included not feeling

their problem was serious enough, independence, not feeling their problem warranted
counseling, or not feeling they had time (Downs & Eisenberg, 2012). Literature showed
that although there may be a general acceptance of mental health and illness within the
community, this acceptance toward others does not always allow an individual to be
comfortable with their own mental health issues (Carmack et al., 2018; Giamos et al.,
2017). This is confirmed in the findings in the current study. Participants had suggestions
for alleviating the stigma by focusing on mental health check-ins rather than encouraging
treatment or illness counseling.
Theme 3, toolbox, related to items or methods participants used to take care of
their mental health. Participants displayed an understanding of their mental health and
had many options for how they addressed it (see Appendix J). This theme relates to the
perceived and actual behavioral control constructs in the TPB (see Ajzen, 2021). Having
an elaborate support system and set of tools can create the perception that mental health
can be controlled, but this is tempered by an individual’s ability to use the tools
(Eisenberg et al., 2012). The tools listed by current participants are broadly supported in
the literature, but the breadth of these interventions appears to be a gap in the literature.
The literature focused on counseling or help seeking rather than self-help tools. The
Caring Campus Project (2018) confirmed some of the tools that were noted by current
participants, but this project was focused on community tools (e.g., formal groups or
clubs). The tools listed in Appendix J are more individually focused and can be done on
one’s own. The information gathered about the tools extends knowledge about
developing individual tools to address mental health. The college students had elaborate

toolboxes and knew the importance of them, but still struggled to use them. This may
indicate the importance of having both community-based and individual tools to support
mental health.
The fourth theme, counseling services, is supported by the literature and extends
the understanding of experiences of participants who needed help and participants’
general knowledge of the services. Participant comments illustrated the importance of
counseling and areas where they found gaps in the counseling service on campus. This
theme relates to the normative belief and subjective norm construct found in the TPB (see
Ajzen, 2021). For example, if a student feels that only those with severe mental health
issues use the counseling services and the normative beliefs make using the counseling
services less acceptable for the average student, the average student will feel less
comfortable accessing them. This was reiterated in the current findings, which showed
that several participants were unable to obtain appointments with counseling services.
Other participants noted that they would not try to schedule appointments because they
felt it was better to save limited services for others.
Participants noted an increase in stress when academic workload was heavier,
which led to the fifth theme of mental health and learning. This theme connects to the
behavioral belief construct in the TPB (see Ajzen, 2021). The belief that studying and
only studying at the expense of overall health was indicated in the interviews and is
confirmed in the literature. Wada et al. (2019) and Lambert et al. (2019) showed a focus
on academic ability that led to a neglect of well-being. Postsecondary students can feel an
immense pressure to achieve academically. Current participants noted the increase of

stress around tests and finals week, which was when academic progress and ability were
being measured. Participants’ comments indicated that the shift at this point was away
from well-being, which led students to choose academics over well-being. Although
several participant comments related to a supportive faculty, the interviews indicated that
students were reticent to take mental health days when they were offered or take
advantage of the options presented by faculty to allow for flexibility.
Limitations of the Study
Although this study was credible and trustworthy, a few limitations were
encountered. One limitation was that the research had to be spread out over two semesters
due to the low response rate during the fall semester. This meant some participants had
been at the college longer and their mental health concerns may have shifted. The data
could have varied from one semester to the next, but the variations did not appear to be
substantial. Another limitation was that one participant was new to the school spring
semester because they had attended a different school in the fall. The final limitation was
there was only one participant who identified as male.
Recommendations
This study contributed to better understanding the cultural norms surrounding
mental health in the individual and within a campus. I explored how and what people
were willing to share with one another and whom they were willing to share with.
Findings showed a community that provided multiple opportunities for connection and
support. Findings also showed a limit in how much participants were willing to share with
one another and people who could support them. Future research could explore historical

language choices surrounding mental health and mental illness and how this impacts
further communication. Another possibility for further research was to explore why
college students appeared unable to accept professors’ attempts to lesson stress
surrounding academics or why that stress remains with a shifting culture. Current findings
indicated this shift and that participants were aware of the shift, but the impact was
unclear. Mental health concerns continue within higher education, and further research
into the nuances may be useful to the overall health of communities.
Another area to explore was a better understanding of why college students
choose not to take advantage of mental health days or other flexible options presented by
professors. Several participant comments provided examples of options faculty gave to
alleviate academic pressure, and participants reported that they would not take advantage
of those options. A better understanding of the barriers to taking advantage of these
options could be explored.
Implications
Positive Social Change
The findings of this study may be used to improve the understanding and
communication of mental health issues in college students at this college. Although the
findings of this study cannot be generalized to all college students, they may contribute to
the wider body of knowledge about this population and mental health. Findings may
assist college staff and faculty in understanding the culture of mental health and
communication issues.

Methodological Implications
I used the TPB framework, which includes the elements of behavior and
normative beliefs and how they impact the attitude or intention toward a behavior (see
Ajzen, 2021). Social constructionism and constructivism were also used to explore the
differences between real and perceived realities, communication, and the relationship to
cultural elements within the community (see Patton, 2014). Mental health may be
explained by this framework in that individuals’ intentions may be to care for their mental
health, but their behavior does not always follow.
Practice Implications
An educational institution lends itself to looking for additional training or types of
training that can impact changes. One learning shift was suggested regarding chemistry,
which was noted by three participants as difficult. One participant suggested extra
scheduled class time for difficult concepts. This is an area that could be explored to
determine whether it could help decrease the stress associated with learning.
There were many comments about the importance of engaged and receptive staff
and faculty (e.g., RAs whom participants did not know compared to RAs who reached
out). Improving hiring and training to increase the number of supportive staff and faculty
may be helpful and improve the overall community health. Participants appeared to
appreciate general reaching as opposed to crisis training. Crisis training was not
addressed in this study and was not mentioned by participants.

Conclusion
Although much has been done to address mental health concerns on the college
campus, students continue to report consistent or increasing mental health concerns
(Healthy Minds Network, 2023). Interviewing participants helped me to understand
cultural norms and how mental health is communicated, perceived, and experienced at a
private religious college in the Midwest by first-year students who live on campus.
Mental health is a personal, intimate aspect of a human being, and taking time to
understand how people can evolve as a culture to ensure better health outcomes may lead
to a higher quality of life for the community. Many lifetime mental disorders start at this
age and can influence mental health policy (L. Chen et al., 2013). A better understanding
how mental health flourishes and is impacted at the traditional college student stage of
life could have important implications for society.

