



216 Final Exam Review Guide
Module 1- Introduction to Health Assessment
1. What are the steps in the nursing process? Be able to identify examples of each step.
Assessment: Obtaining subjective and objective data
Diagnosis: Nursing diagnosis analyzes the data collected, identifying actual and
potential problems.
Planning: Using SMART to create a plan based off data and diagnosis
Implementation: Use skills to implement appropriate therapeutic interventions.
Evaluation: Monitor the effectiveness and achievability of goals and the need for
intervention or adjustment
2. What are the components of the general survey?
Physical Appearance
Body structure
Mobility/Gait
Behavior
Speech
Dress, hygiene, grooming, and odors (body, breath)
Vital signs with asking about Pain
3. What types of questions may be asked in the review of systems?
Start with the head all the way down to toes and ask relevant questions that are
age-appropriate for each system
oIntegumentary
oHead, neck, cognitive
oEyes, ears, nose, mouth
oRespiratory
oCardiovascular
oGI
oGU
oMSK
oNeuro
oEndocrine
oMental
4. What are the four techniques used in physical assessment?
Inspection
Palpation
Auscultation
Percussion
5. What are the techniques used when assessing the abdomen?
Inspection
Auscultation
Palpation
6. How do you properly palpate for temperature?
With the dorsal side of the hand
7. What is each side of the stethoscope called and used for?

Diaphragm: used for high pitched
Bell: Low pitched (heart murmur)
Module 2- General Survey
1. What are the vital signs you typically need to collect from every patient?
Temperature 96.8-100.4F
Pulse 60-100 bpm
Respiration rate 12-20 bpm
Pulse Ox 95-100%
Blood pressure <120 / <80
oHypotension <90 / <60
oHypertension >130-140 / 80-90
2. Be able to identify the most common pulse points.
Radial (or thumb side of the wrist)
3. What are the different ways to take a temperature? What is the technique for each one?
Oral
Rectal -- sims position with upper leg flexed. 2.5-3.5 cm (1-1.5 inches) for adult.
Axillary
Tympanic -- Pull the ear up and back (for adults) or down and back (for a child)
Temporal
4. Which sources are considered core and surface temperatures?
CORE = Oral and Rectal
SURFACE = Axillary, Tympanic, and Temporal
5. What are some causes of out-of-range vital signs?
Exercise, Medication, smoking, lifestyle habits, drinking a cold drink, food,
diseases, conditions, hormonal changes, stress, ect.
6. How do you perform a two-step blood pressure?
Palpate brachial pulse, wait 30 secs, place diaphragm and up 20 above, let out
pressure
7. What are the stages of hypertension?
Hypotension: <90 systolic, <60 diastolic
HTN 1: 130 - 139 sys, 80-90 diastolic
HTN 2: >140 sys, > 90 diastolic
8. How do you describe the behavior and effect of a patient?
AOX4
Questions you ask --> Name, DOB, Location, Situation
oOrientation needs to know where they are, who they are and time
9. Be able to differentiate between mobility, posture and body structure.

Mobility: ability to move
Posture: the position in which someone holds their body when they are sitting or
standing
Body structure: a particular complex anatomical part of a living thing
10. What does each BMI range represent?
Less than 18.5 is underweight
18.5-24.9 Normal BMI
25-29.9 overweight
Obese 30 or greater
11. When is a focused assessment appropriate? A full physical examination?
Focused assessment: focuses on a particular topic, body part, or functional ability
rather than an overall health status
Physical exam: uses techniques of inspection, palpation, percussion, auscultation
(head to toe assessment)
Module 3- Health History
1. What questions would you ask to obtain a complete health history from a patient?
Childhood illnesses, chronic illness, hospitalizations, surgeries, immunizations,
examinations, screenings, allergies
2. What is the difference between subjective and objective data? How do you collect each?
Subjective = symptoms (only what the pt an tell you how they feel)
oPain scale, Feelings, Symptoms
Objective = what you can see (5 senses) and observe
oVital signs, Bruises/cuts, Assessment
3. What is an open-ended question? When is it most appropriate to use them?
Open-ended questions are not yes or no questions
oTell me more about...
Useful when you need to probe but respectfully for more information
4. What question types would you want to avoid?
Close ended questions/Yes or no
5. What is a functional assessment?
Determines the pt’s ability to care for themselves
oAre they able to do things for themselves (physically, mentally)
oADL’s
6. How does culture influence a patient’s health?
FICA
oF = Faith
oI = Influence
oC = Community
oA = Address preferences
7. What is the history of present illness (HPI) assessment?
Description of the development of the pt’s present illness --> S/S
oOLD CART
O = Onset
L = Location
D = Duration

C = Characteristics
A = Aggravating and Alleviating Factors
R = Related symptoms
T = Treatment
S = Severity
Health Assessment Modules 4-5 Review
1. What findings would lead a nurse to suspect abuse?
Examine all body surfaces for signs of physical abuse
Bruises, burns
Assess for injuries of abuse
Black eyes, facial injuries
2. What areas are at highest risk for pressure related skin breakdown?
Bony prominences - areas where bones are close to the surface
3. What categories are assessed in the Braden Scale?
For predicting pressure sore risk
Sensory Perception 1-4
oAbility to respond meaningfully to pressure related discomfort
Moisture 1-4
oDegree to which skin is exposed to moisture
Activity 1-4
oDegree to physical activity
Mobility 1-4
oAbility to change and control body position
Nutrition 1-4
oUsual food intake pattern
Friction and Shear 1-4
oMovement in bed/sheets
SEVERE RISK: Total score 9
MILD RISK: Total score 15-18
4. What assessment findings would indicate dehydration?
Poor indicates possible dehydration, increased risk for skin breakdownturgor
oPoorly hydrated skin retains the tent shape of the pinched skin
Weak and rapid pulse
Hypotension
5. Who should perform foot care on a diabetic?
Podiatrist
6. What are age-related changes associated with the integumentary system?
Skin -- Thinning, drier
Loss of elasticity
Slow wound healing
Decline in glandular structure and function (less oil, moisture, sweat)
7. What should a diabetic patient be educated on regarding foot care?
Inspect feet daily
Use lukewarm water/dry thoroughly
Clean cotton socks daily
Comfortable shoes that don’t restrict circulation
8. What are the functions of the skin?
Protect the inner body parts and organs
Body temperatures regulation through shivering and sweating
Sensory perception of temperature, touch and pain
Produce vitamin D
First line of defense
9. What assessment findings would a nurse expect with a patient with liver failure?
Jaundice- yellow to orange color
oA slight yellow tinge can be an expected finding for client who have dark
skin
oCan be found in
Skin, sclera, mucous membranes
10. What patients are at an increased risk for developing a pressure ulcer?
Thinner skin (due to age)
Poor nutritional state, which affects healing
Presence of moisture due to incontinence, wound drainage or perspiration
Immobility
11. What is herpes zoster (shingles)? What findings would you expect with a patient with
herpes zoster?
Herpes zoster – shingles
oCommon viral infection that erupts years after exposure to chickenpox and
invades a specific nerve tract
Findings
oPain, Itching, Tingling, Burning along the involved dermatome
12. What is the ABCDE skin assessment? What is it used to assess?
Check lesions system tousing the ABCDE detect possible skin cancer
A – A symmetry of shape
B – B order irregularity
C – C olor variation within one lesion
D – D iameter greater than 6mm
E - E volving or changing in color, elevation, shape, size, itching, crusting or
bleeding
13. What are the signs and symptoms of anemia?
Anemia: Reduced hemoglobin and poor circulation
oS/S
RR increased and depth
Pallor – loss of pink or yellow skin
Weakness
SOB
Cold hands and feet
Tachycardia (increased heart rate)
14. What is the best way to assess jaundice in a dark-skinned patient?
Jaundice -- A slight yellow tinge
oYellow coloring of the sclera
On the palms and soles
15. What would you describe pallor in a patient with dark skin?
In black skin tones
oA change to gray, particularly in the mucous membranes
In brown skin tones
oA change to yellow brown
Observe by inspecting the color of the lips, mucus membranes, nailbeds
16. How do you assess a patient for pitting edema?
Pitting edema is present when pressure on the affected area leaves a visible
indentation in the skin.
4 points scale is used to document the degree of pitting edema
o1+ = Trace, 2mm, rapid skin response
o2+ = Mild, 4mm, 10 to 15 second skin response
o3+ = Moderate, 6mm, prolonged skin response
o4+ = Severe, 8mm, prolonged skin response
17. What is purulent, serous, serosanguineous, and sanguineous fluid?
Serous – Clear
Serosanguineous – Both blood and liquid part of blood (serum)
Purulent – Contains leukocytes and bacteria
oIndicate infection
Sanguineous – Contains red blood cells, red and bloody
18. What patients would be at the highest risk for developing malignant melanoma?
“Ugly ducklings” skin – client who has many nevi (moles)
The risk of melanoma increases with each additional sunburn
19. What are some interventions to prevent pressure ulcers?
Inspect the skin daily for signs of breakdown
Reposition every 2 hours
Elevate the head of the bed no more than 30 degrees to prevent a shearing injury
Remove sources of excessive moisture due to incontinence, drainage, diaphoresis
Keep skin clean, dry and intact
20. How would you describe vesicles, bullas, papules, and wheals?
Vesicles: Raised, fluid filled
oSmall superficial, filled with serous fluid
oEx: Blister, herpes simples, varicella (chicken pox), shingles, acute
eczema
Bullas: small superficial, filled with serous fluid
oEx: blister, medication reaction
Papules: Primary lesion, raised lesion – small < 1cm area
oPalpable, circumscribed, solid elevation of the skin
oEx: Elevated mole, wart, skin tag
Wheals: Irregular area of edema on the skin
oRaised solid area, Palpable, irregular borders, edematous
oEx: Insect bite, allergic reactions, hives
21. What would you expect to see on assessment in a patient who has a wound infection?
Erythema and swelling around the wound
Fever, warmth of the surrounding soft tissue
Foul odor
22. How would you describe a stage 1, 2, 3, and 4 pressure ulcers?
Stage 1: Reddened area that does not blanch with pressure
oNon-blanchable erythema of intact skin:
Stage 2: Partial loss of dermis
oInvolves epidermis and dermis
oThe wound bed is viable with reddish-pinkish bed without slough, eschar,
granulation tissue, or adipose tissue
Stage 3: Full thickness skin loss with damage or necrosis to subcutaneous
tissue
oVisible adipose tissue with possible granulation tissue and epibole (wound
edges appear rolled under), some slough, eschar present.
Possible undermining or tunneling.
Stage 4: Full thickness of skin loss resulting in exposed bones, tendons /
muscles
oSkin and tissue loss with cartilage, bone, fascia, muscle, ligaments, or
tendon exposed in the wound or easily palpable
Epibole, tunneling, and undermining are common
23. How do you perform a whisper test?
Whisper test (CN VIII)
oTechnique- occlude one ear and test the other to see if the client can hear
whispered sounds without seeing your mouth move
24. What is a Snellen chart used for? What does the top and bottom number indicate?
Snellen chart:
oUse to screen for myopia (impaired for vision)
oTop number: The distance (in feet) the client stands from the chart
oBottom number: The distance at which a visually impaired eye can see
the same line clearly
For clients who can’t read
25. What is the Weber test?
Weber test: Auditory screening test (ears)
oTechnique: Place a vibrating turning fork on top of the client’s head.
oThey should be able to equally hear sound with both ears
26. When assessing lymph nodes on a healthy patient, what would you expect?
There should be no lumps or swelling visible or palpate in the neck, no
tenderness, no enlargement nodes
27. How do you assess accommodation on a patient?
Accommodation of the pupils when they dilate to look at an object far away and
then converge and constrict to focus on a near object
oFollow pen light to nose
28. When performing an otoscopic examination, what are some expected and unexpected
findings?
Expected findings:
oThe auricle, or outer ear, should appear symmetric in size placement
oThe color of the client’s ear should be the same as the client's face, should
be intact, with no lumps, edema, or lesions

o Cerumen can be wide variety of colors and textures from grey, yellow to
tan to black moist and waxy to dry and flaky.
Unexpected findings:
o Redness of the client’s ears is a sign of inflammation / fever
o Redness, edema, and purulent, or crusty drainage of the ear canal can
indicate an infection
o Bright red blood or watery discharge following a trauma can indicate a
fracture to the base of the skull
29. What tool would be used when performing an examination of the tympanic membrane?
Otoscope
30. What teaching should be done for a patient who is at risk for falls due to vision
impairment?
Maintaining adequate lightning
Keeping the call light within reach
Ensuring that the path to chair and bathroom are clear
31. When caring for a patient with hearing loss, what should the nurse assess first?
Assess client's ability to hear various frequencies (high vs low pitch) at various
decibels (soft vs loud tones)
32. What are the expected findings for a head and neck examination for the older adult
patient?
ROM in the head and neck may be limited because musculoskeletal changes or
osteoarthritis
33. How should the nurse palpate for lymph nodes of the neck?
Use the pads of the index and middle fingers and move the skin over the
underlying tissue in a circular motion to try to detect enlarged nodes.
o Compare from side to side, one at a time
34. How should an otoscopic examination be performed on an adult patient?
Pull up and back adults down and back for childrenon the auricle of adults ( )
oUsing the otoscope, slightly down and forward 1 to 1.5 cm, following but
not touching the ear canal to visualize
35. When assessing a patient’s pupils with a penlight, what would the nurse expect to find?
Pupils should be black, round, regular, and equal in size with the iris clearly
visible.
oPERRLA
36. When assessing pupil size, what size of pupils are expected?
Normal adult pupil size
o3-5 mm
PERRLA- uses CN II, CN III
oP - Pupils clear
oE - Equal
oR - Round
oRL - Reactive to Light
Both directly and consensually when you direct light into one pupil
and then the other
oA - Accommodation
Of the pupils when they dilate to look at an object far away and
then converge and constrict to focus on a near object
37. What vision tests for central vision acuity?
Snellen chart
Rosenbaum chart
38. How is the Rosenbaum vision test performed?
Hold chart 14 inches from the client’s face to screen for presbyopia (impaired
near vision or farsightedness). Visual Acuity
39. What are the causes of conductive hearing loss?
Ear infections, Obstruction, Wax Accumulation ( ), Cerumen Tympanic
Membrane Perforation (Ear drum damage), Otosclerosis (Abnormal bone growth
in ear)
40. How should the nurse perform an assessment of the thyroid?
Inspecting: Inspect the lower half of the neck. Have the pt hyperextend the neck.
Instructing: Instruct pt to take a sip of water and feel the thyroid gland as it
moves up with the trachea.
Palpating: Palpate thyroid gland on both sides
Auscultation: If the thyroid is enlarged, auscultate it.
oA indicates an increase in blood flow to the area, possibly due to bruit
hyperthyroidism
41. *A patient should be instructed to sleep with an artificial eye in place to keep the
socket stable and healthy. *
42. Which cranial nerves are associated with HEENT and how do you test their function?
CN I Olfactory -- – Sense of smell
oHave patient smell a scent
CN V Trigeminal – –
oHave patient bite down
oTouch - rub the side of the jaw to see if they detect the sensation.
CN VII Facial – –
oPuff up their cheeks and raise their eyebrows.
oAsk patients to use different facial expressions
CN XI Accessory Spinal- -
oPress down the pt shoulders while they are shrugging to test their
resistance
oTurning head from side to side
Examination Test Terms:
Rinne - Hearing/Place in front of ear and mastoid process
Diplopia – Double vision
Myopia - Near sided
Carinal Nerves
CN I Olfactory
oSmell

CN II Optic
oVision --> Snellen chart
CN III Oculomotor
oEye movement
oControl of pupil diameter
CN IV Trochlear
oEye gaze down and up
CN V Trigeminal
oBiting down
oClose eyes for touch to face
CN VI Abducens
oGaze laterally (side to side)
CN VII Facial
oDifferent facial expressions
oStick out tongue
CN VIII Vestibulocochlear
oHearing --> Weber's test
CN IX Glossopharyngeal
oMouth movement of soft palate and gag reflex
oSwallowing and speech quality
oTaste
CN X Vagus
oMouth movement of soft palate and gag reflex
oSwallowing and speech quality
CN XI Accessory
oResistance to shoulder shrug (sternocleidomastoid)
CN XII Hypoglossal
oAssess tongue for movement and strength
CN Acronym
▫Oliver = lfactory o
▫Often = optic
▫Orbits = oculomotor
▫Through = trochlear
▫The = trigeminal
▫Atmosphere = abducens
▫For = acial f
▫Very = vestibulocochlear
▫General = glossopharyngeal
▫Vape = vagus
▫And = accessory spinal
▫Herion = hypoglossal
Module 6 - Respiratory

1. What breath sounds would you expect to hear with an asthma attack?
Wheezes: are whistling, high-pitched musical sounds
2. What are r? What do they sound like?
Popping: when alveoli are not opening enough. Popping sound at the end of the
breath
3. What are bronchovesicular, bronchial, and vesicular breath sounds? Where would they
be heard?
Bronchovesicular breath sounds: Heard over right and left major bronchi
Bronchial breath sounds: Heard to the right and left of trachea and larynx
Vesicular breath sounds: Auscultated over anterior and posterior chest wall
oHeard from clavicle to lower rib change
oSounding like wind blowing through trees
4. What is central cyanosis? Where would we assess for this?
Central cyanosis --> associated with Hypoxia
oA blue-gray coloration
oCentral = found on head, neck, trunk
Assess: Lips, tongue, mucous membranes, facial features, nail beds, Extremities,
hands, feet
5. What are Cheyne-Stokes respirations?
Cheyne-Strokes Breathing: appears to have a “start-stop” pattern, become faster
and deeper than normal, then slower, progress of apnea
oSeen at end of life
6. What assessment findings would you expect in a patient with COPD?
S/S of COPD
oCoughing
oBarrel chest
Rounded, bulging chest that resembles the shape of a barrel
oWheezing
oPursed-lip breathing
oClubbed fingers
oCyanosis
oHypoxia
oDyspnea
7. What is the most common cause of COPD?
Long-term smoking
8. What lung sounds would you expect to hear with pneumonia?
Crackles: rattling, crackling, popping or bubbling sound
9. What lung sounds would you expect to hear with croup?
Stridor: High-pitched crowing or animal (screeching) sound
oResult of upper airway obstruction
oSeen in kids or adults with Croup
10. What factors could interfere with your ability to assess lung sounds?
Clothing, Body hair, Your own hand, Your own breathing
11. What are Kussmaul’s respirations?
Kussmaul respirations: Increased RR, Regular pattern, abnormally deep
12. What would you expect to hear when auscultating a plural friction rub?
Pleural Friction Rub: coarse, grating tone like rubbing two pieces of leather
together
13. What respiratory tool should be used for post-op patients to prevent atelectasis and
pneumonia?
Reposition every 2 hours. Deep breath and cough exercises. Incentive Spirometers
Atelectasis: collapse of alveoli due to hyperventilation, airways blocked by
mucous plugs, immobility
Pneumonia: inflammation of the alveoli due to infection with bacteria or viruses,
toxins, or irritants
14. What is pursed lip breathing? What patients would this type of breathing benefit?
Pursed Lip Breathing: mechanism used to prolong expiration, help expel trapped
air and keep alveoli open longer for maximum oxygenation of pulmonary blood.
(COPD, Asthma)
15. When preparing to do a respiratory assessment, what should the nurse do first?
Inspect / observe first
oThen palpate / percuss and auscultate
16. What are rhonchi? How does it sound like?
Rhonchi: continuous snoring-type sound
oCause by fluid, mucus, or a growth in larger airways
17. What is the first thing we should do when a patient is experiencing shortness of breath?
Rise the head of the bed to a Semi-Fowlers position
18. What can we encourage the patient to do to thin respiratory secretions?
Encourage fluid intake, Humidifier, IS, deep breathing exercise
19. How can we prevent respiratory post-surgical complications?
ICOUGH
oI = S Incentive Spirometer I
oC = ough & Deep Breathe C
oO = Oral Care
oU = nderstanding (patient education)U
oG = et out of bedG
oH = ead of bed elevated 90 degrees (High Fowler's) when eating H
Deep breathing treatments
Module 7 – Cardiovascular
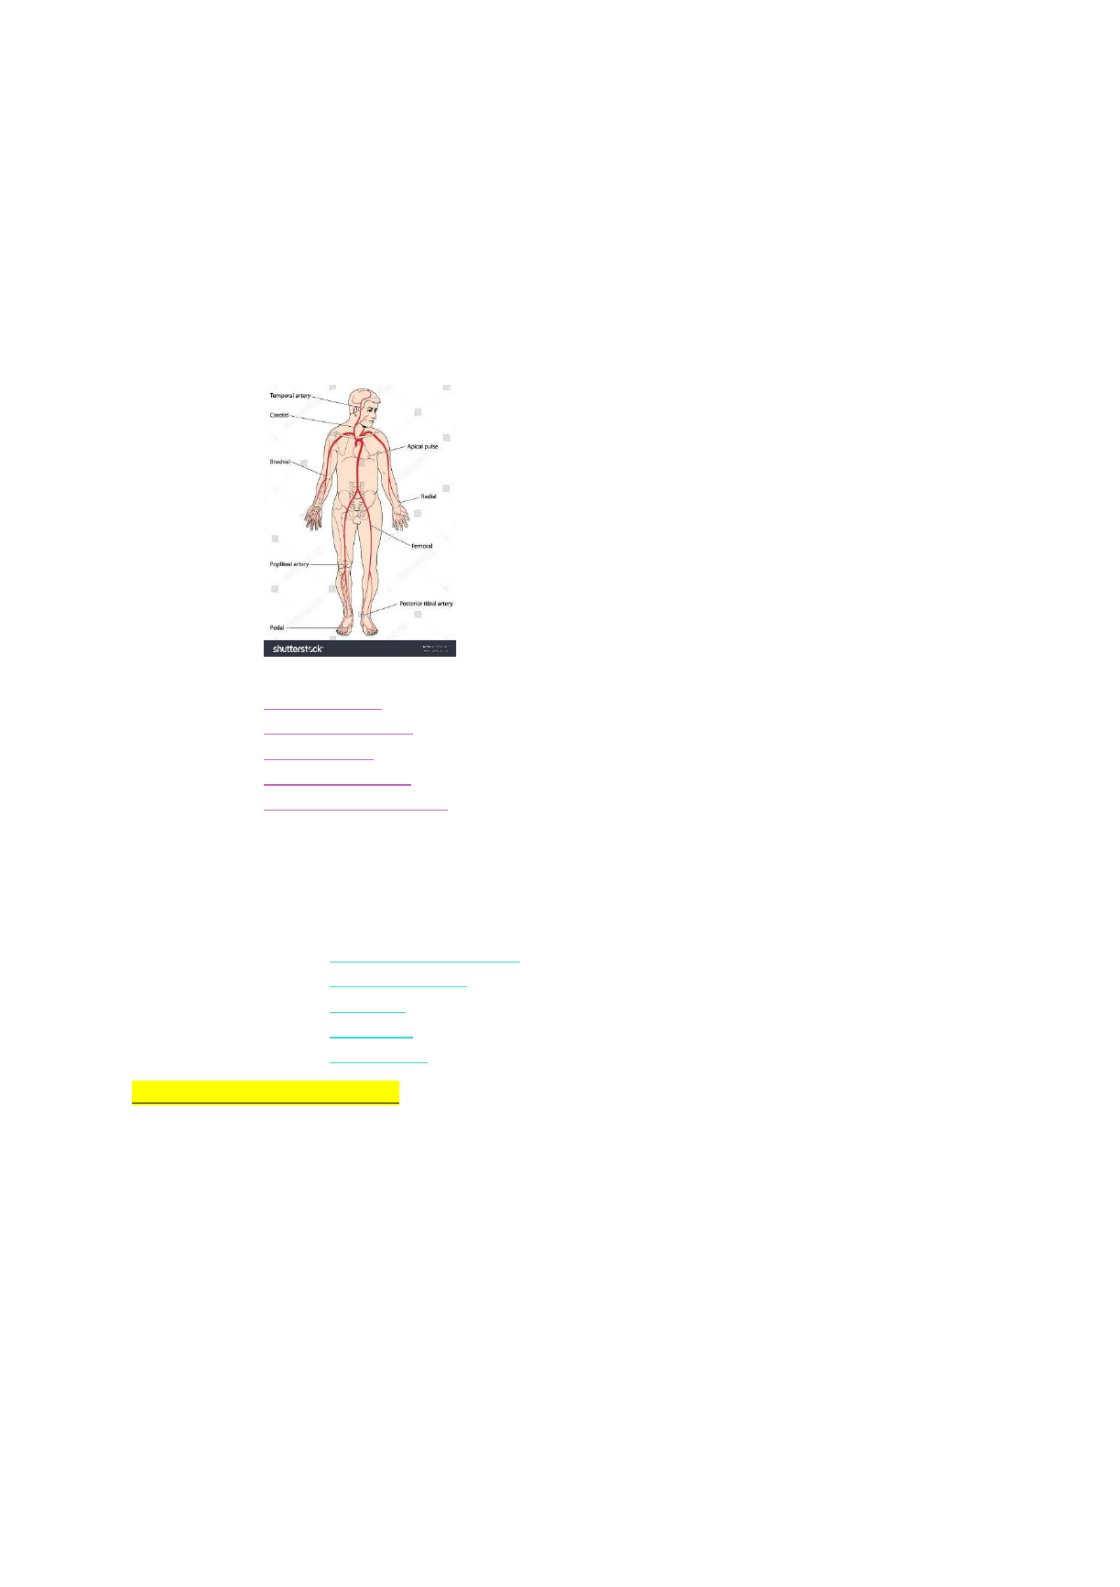
1. Where should you access the apical pulse?
Medial to the left midclavicular line at the 5th ICS
2. Where should the nurse assess for the dorsalis pedis pulse?
On the top of the foot, along a line with the groove between the extensor tendons
of the first and second toes.
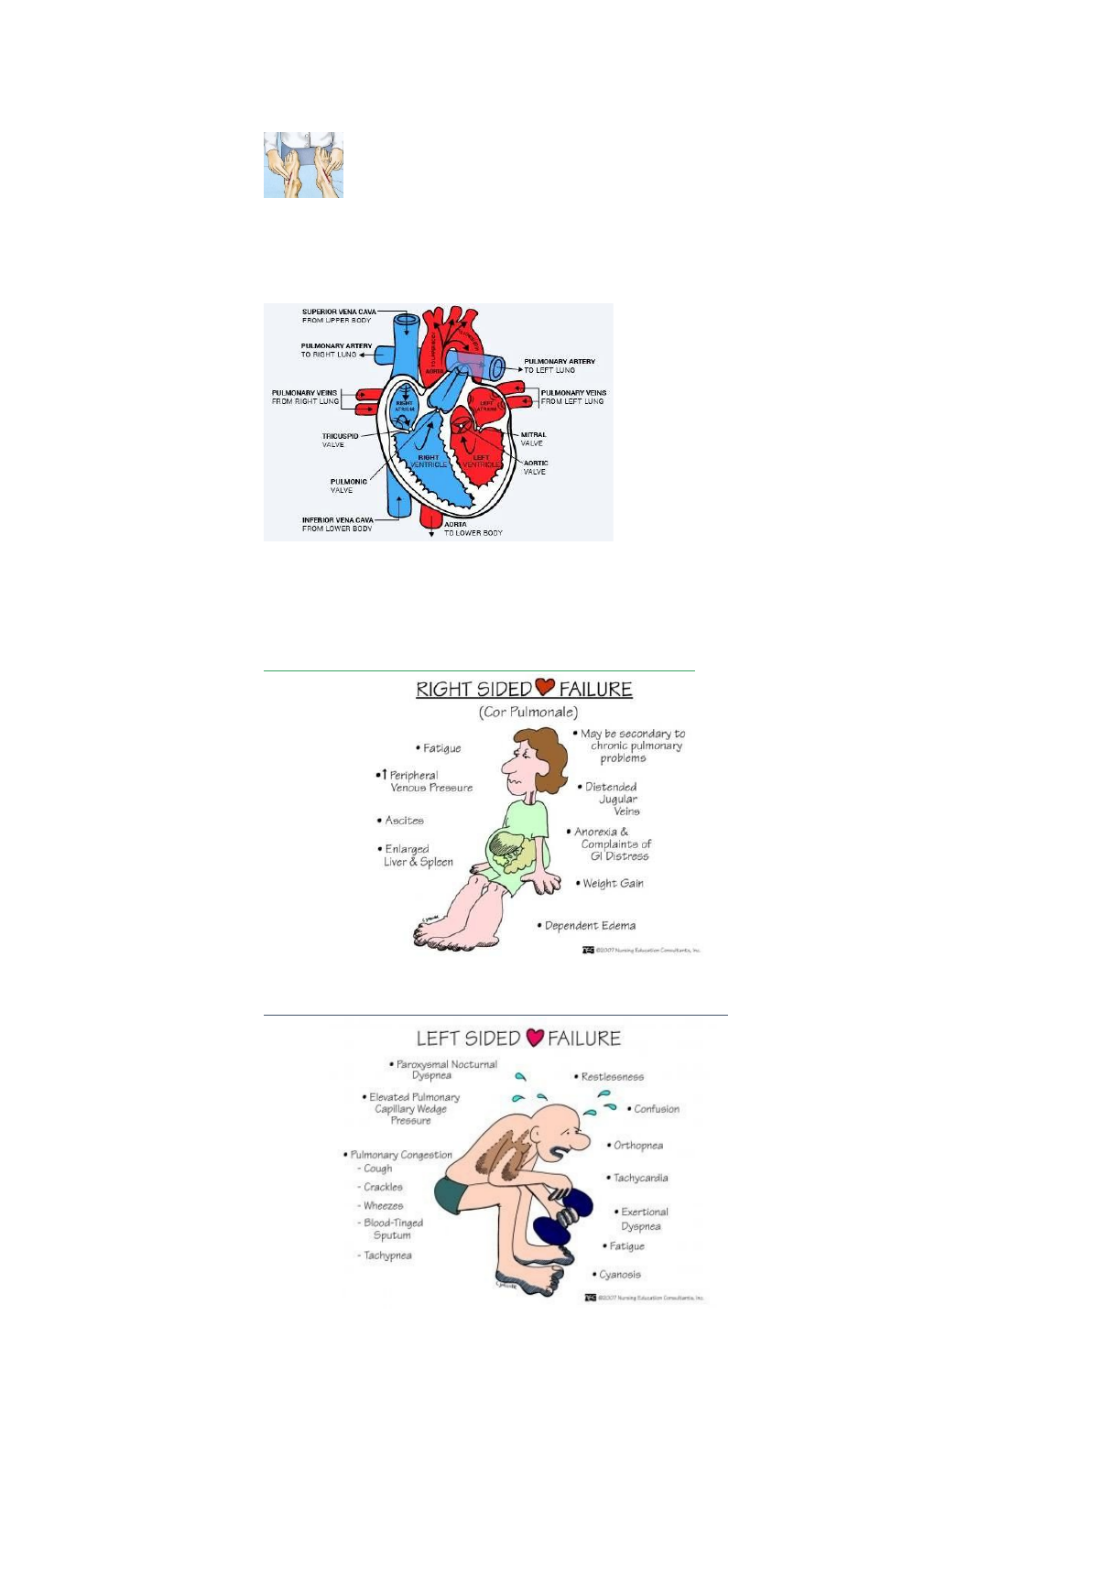
3. What is the order of blood flow through the heart?
Superior/Inferior Vena Cava (from the body) --> Right Atria --> Tricuspid
Valve --> Right Ven --> Pulmonic Valve --> Left Atria --> Mitral Valve -> Left
Ventricle -->Aortic Valve --> Aorta (to the body)
4. What do we worry about when a patient has orthostatic hypotension?
Decreased blood pressure when changing position from standing, sitting, or lying.
oFall risk due to dizzy spells
5. What are the S&S of right-sided heart failure?
If not pumping well, blood backs up in the body
o
6. What are the S&S of left-sided heart failure?
If not pumping well, blood backs up in the left lung
o
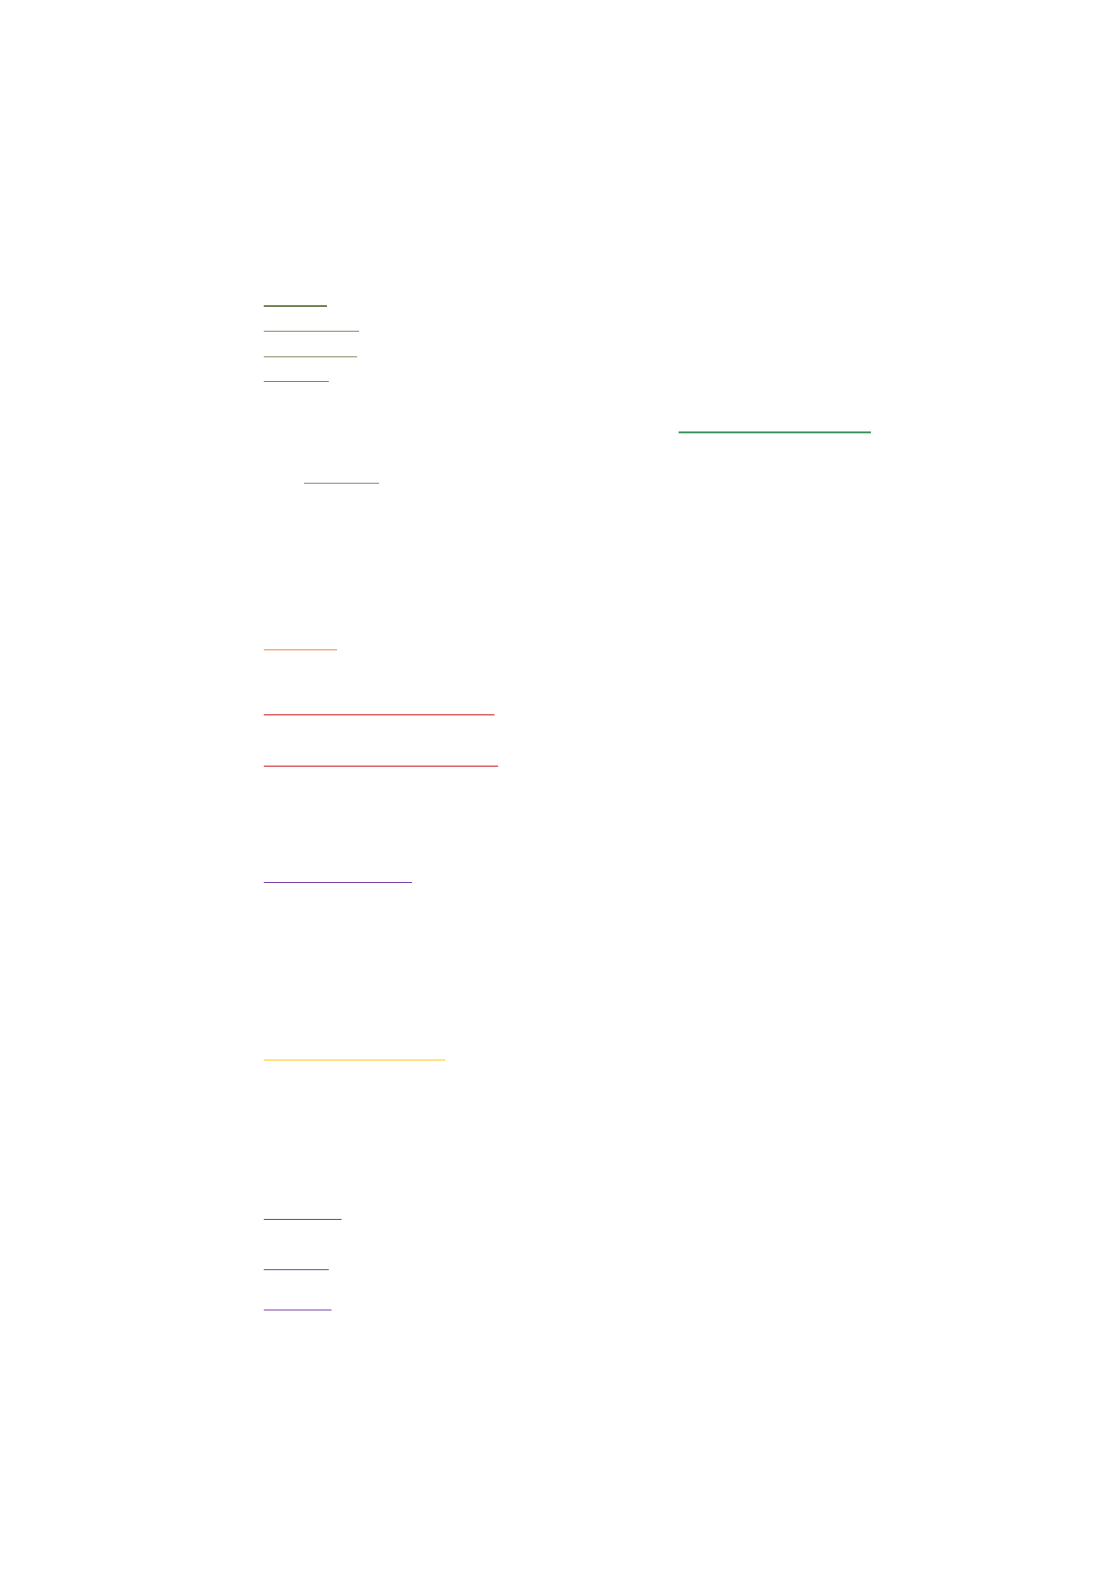
7. What are risk factors for cardiovascular disease?
Family History
High BP
Cholesterol Levels
Lifestyle Habits
8. Where are the aortic, pulmonic, tricuspid, and mitral valves heard? Know the landmarks.
Aortic: Just right of the sternum at the 2nd ICS (Intercostal space)
Pulmonic: Just left of the sternum at the 2nd ICS
Tricuspid: Left 4 ICS just lateral to the sternum
th
Mitral: Left midclavicular line at the 5th ICS
9. What is sinus tachycardia?
An SA node that is sending electrical impulses greater than 100/min
10. What is the primary pacemaker of the heart called?
The SA node (1 node), Located in the right atrium,
st 60-100 bpm
11. What are the S&S of inadequate circulation?
Long capillary refill
Cold hands
Pale skin
12. What tool can the nurse use if they are unable to palpate peripheral pulses?
Doppler
13. What is a peripheral venous ulcer? What is a peripheral arterial ulcer?
Peripheral Venous Ulcer: Insufficient blood returns to the heart, damage to the
veins
Peripheral Arterial Ulcer: Lack of blood flow to the arteries. Damage to the
arteries
14. How would a nurse document a normal pulse in the medical record?
+1 weak pulse
+2 normal pulse
+3 strong pulse
+4 bounding pulse
15. How should the nurse assess JVD?
Elevate head of bed to 30- to 45-degree angle, turn neck to the side. Shin a light at
vein to see if it is distended
16. What order does the blood flow through the valves of the heart?
Toilet Paper My Ass
oT T = ricuspid valve
oP = Pulmonary valve
oM = Mitral valve
oA A = ortic valve
17. What does a murmur sound like?
Murmur = Blowing or swishing
18. Where is the best place to assess S1 ? S2 ? (lub) (dub)
S1 Lub -- Is valve (4 intercostal) and valve (5 intercostal)tricuspid th mitral th
S2 Dub -- Is valve (2 intercostal) and valve (3 intercostal)aortic nd pulmonic rd

19. Where is the apical pulse located?
5 th
intercostal space at the left midclavicular line.
20. What are the early signs of hypoxia?
RAT = early hypoxia
oR = Restless
oA = Anxiety
oT = Tachypnea/Tachycardia
Hypertension
21. What are chronic signs of hypoxia?
Bed = late hypoxia
oB = Bradypnea/Bradycardia
oE = Extreme Restlessness
oD = Dyspnea (severe)
Clubbing
Hypotension
22. What is the heart’s conduction system?
Save A Bunny Rabbit Please
oS S = inoatrial (SA) node. 60-100 bpm
oA = Atrioventricular (AV) node. 40-60 bpm
oB B = undle of His
oR R = ight and Left bundle branches
oP P = urkinje fibers. 20-40 bpm
Last resort to keep going
23. Heart Sounds?
S1 = Lub = closing of tricuspid/ mitral valves
S2 = Dub = aortic/ pulmonic valve closure
S3 = may be heard in adolescents
24. Know circulation?
Arteries – blood from heartery
Vein – bring back in for oxygen
Module 8 – Abdomen
1. What organs are in the left lower quadrant, left upper quadrant, right lower quadrant,
right upper quadrant?
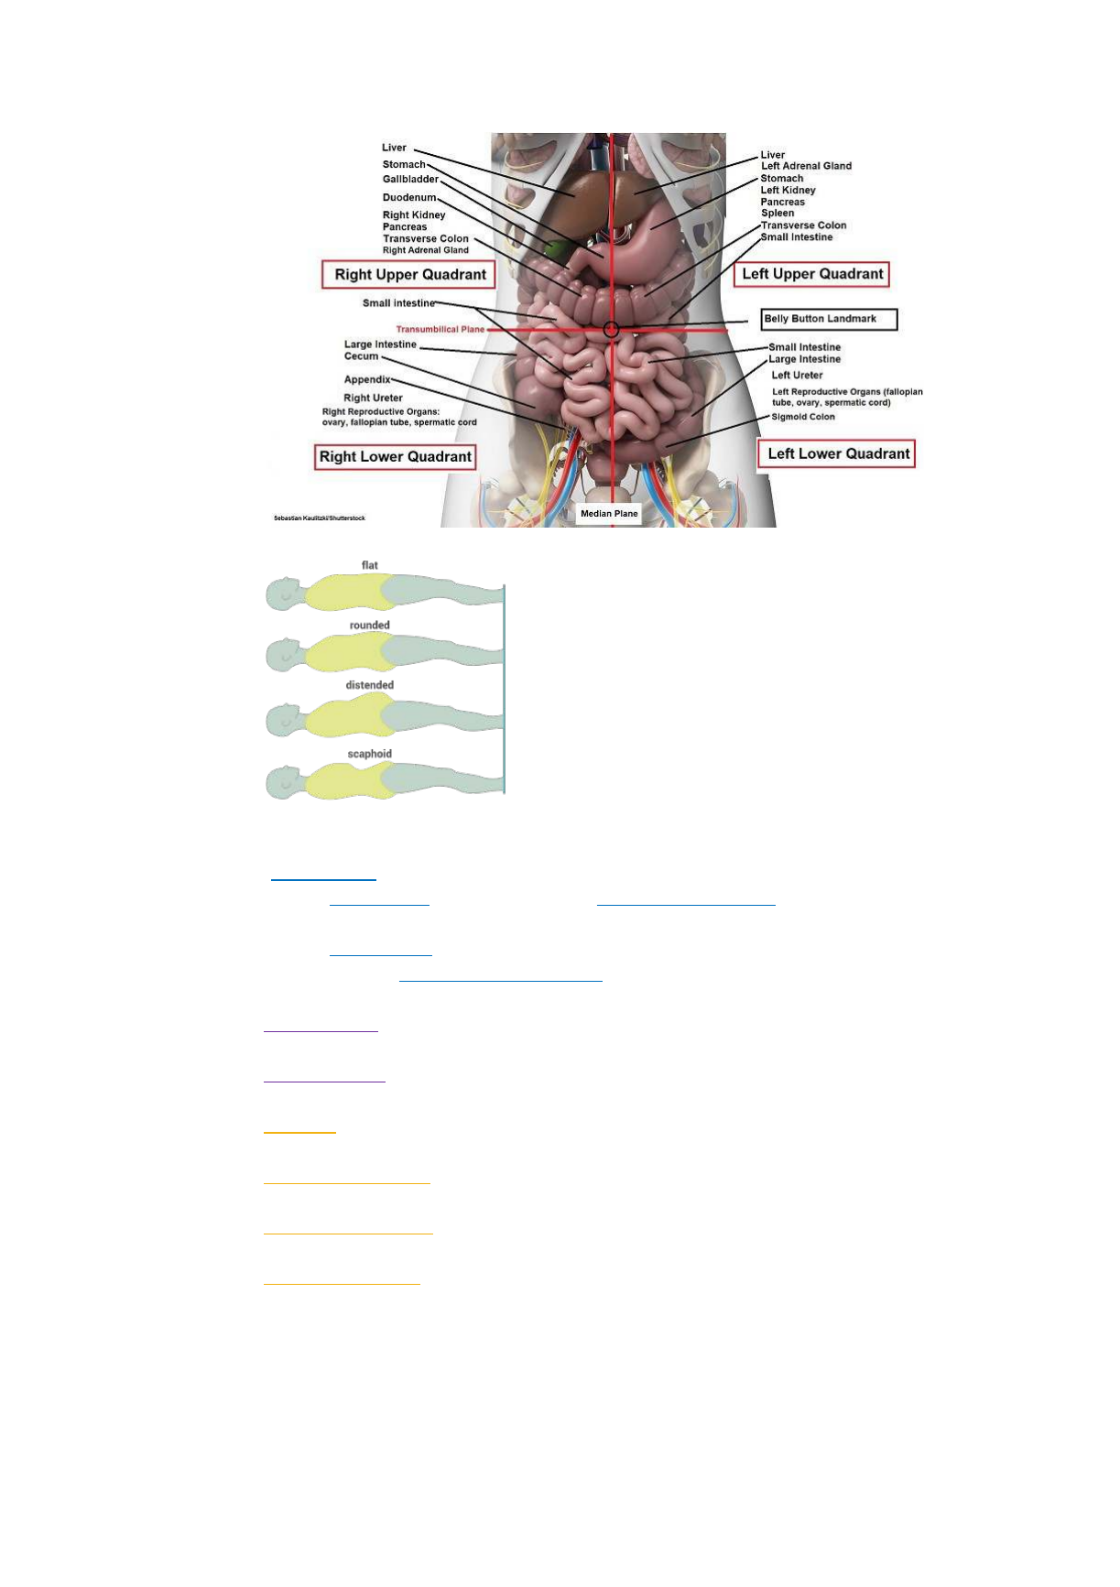
2. What are the different abdominal shapes?
Flatus: The protrusion is mainly midline, No change in the flank
3. When is it normal to see abdominal aortic pulsations?
(Consensus: in thin adults it’s normal)
oPeristalsis: wavelike motions visible in thin adults or in patients with
intestinal blockages.
oPulsations: Regular beats of movement midline above umbilicus (belly
button) expected in thin adults, pulsating mass is unexpected.
4. What are the causes of hypoactive and hyperactive bowel sounds?
Hypoactive: Decreased bowel sounds
oAbsent bowel sounds, diminished, soft sounds that occur less than 1 min
Hyperactive: Increased bowel sounds, Loud growling sounds (borborygmi)
5. What is an umbilical hernia, incisional hernia, and inguinal hernia?
Hernia: Is when the abdominal viscera protrude through the muscle wall of the
abdomen
Umbilical Hernia: Is an outward bulging due to delayed closure around a small
muscle around the umbilicus (belly button)
Incisional Hernia: Is an protrusion of tissue, intestine, organ that forms at the site
of a healing surgical scar
Inguinal Herina: It is a bulge that occurs in the groin region, with weakening of
muscles in the lower abdomen

6. What are expected variations and unexpected findings during inspection of the abdomen?
What causes them?
Expected Findings: Eye level with abdomen helps.
oSmooth and even skin. Silver striae aka stretch marks (rude). Healed
scares. Moles ( )nevi
Unexpected:
oDilated veins, Jaundice, Cyanosis, Redness, Ascites, Scars, lesions,
7. What assessment findings would we see in a patient with pancreatitis? Cholecystitis?
Appendicitis? Ascites?
Pancreatitis: Inflammation of the pancreas. LUQ
Cholecystitis: Gallbladder infection. RUQ
Appendicitis: Inflammation of the appendix. RLQ
Ascites: Distended stomach due to fluid retention, possible reflect cirrhosis
8. What symptoms are consistent with duodenal ulcer?
Duodenal Ulcer: Is a peptic ulcer that develops in the first part of the small
intestine (duodenum)
Peptic Ulcers: Are open sores that develop on the inside lining of the stomach and
upper portion of small intestine
9. What is an early sign of a paralytic ileus?
Paralytic Ileus: ---> intestinal obstruction. A cessation of bowel peristalsis
S/S:
oDistended abdomen, Fullness, Gas, Abdominal spasms, Constipation or
diarrhea, Nausea, Foul smelling breath
10. What is the priority for a patient who has just had a GI endoscopy?
GI Endoscopy: Esophageal to stomach endoscopic imaging technique
oAssessing chest pain, bleeding, fever, abdominal pain, vomiting
Module 9 – Musculoskeletal & Neurological
1. Know anatomical positions and joint movement terminology.
Fibrous joint: Immovable, no joint cavity
Cartilaginous: Not highly movable, no joint cavity
Synovial: Moveable, all limb joints and most joints of the body
Joint Movement Synovial Joints / with example & movement ( )
oPivot
oHinge
oCondyloid
oSaddle
oBall and Socket
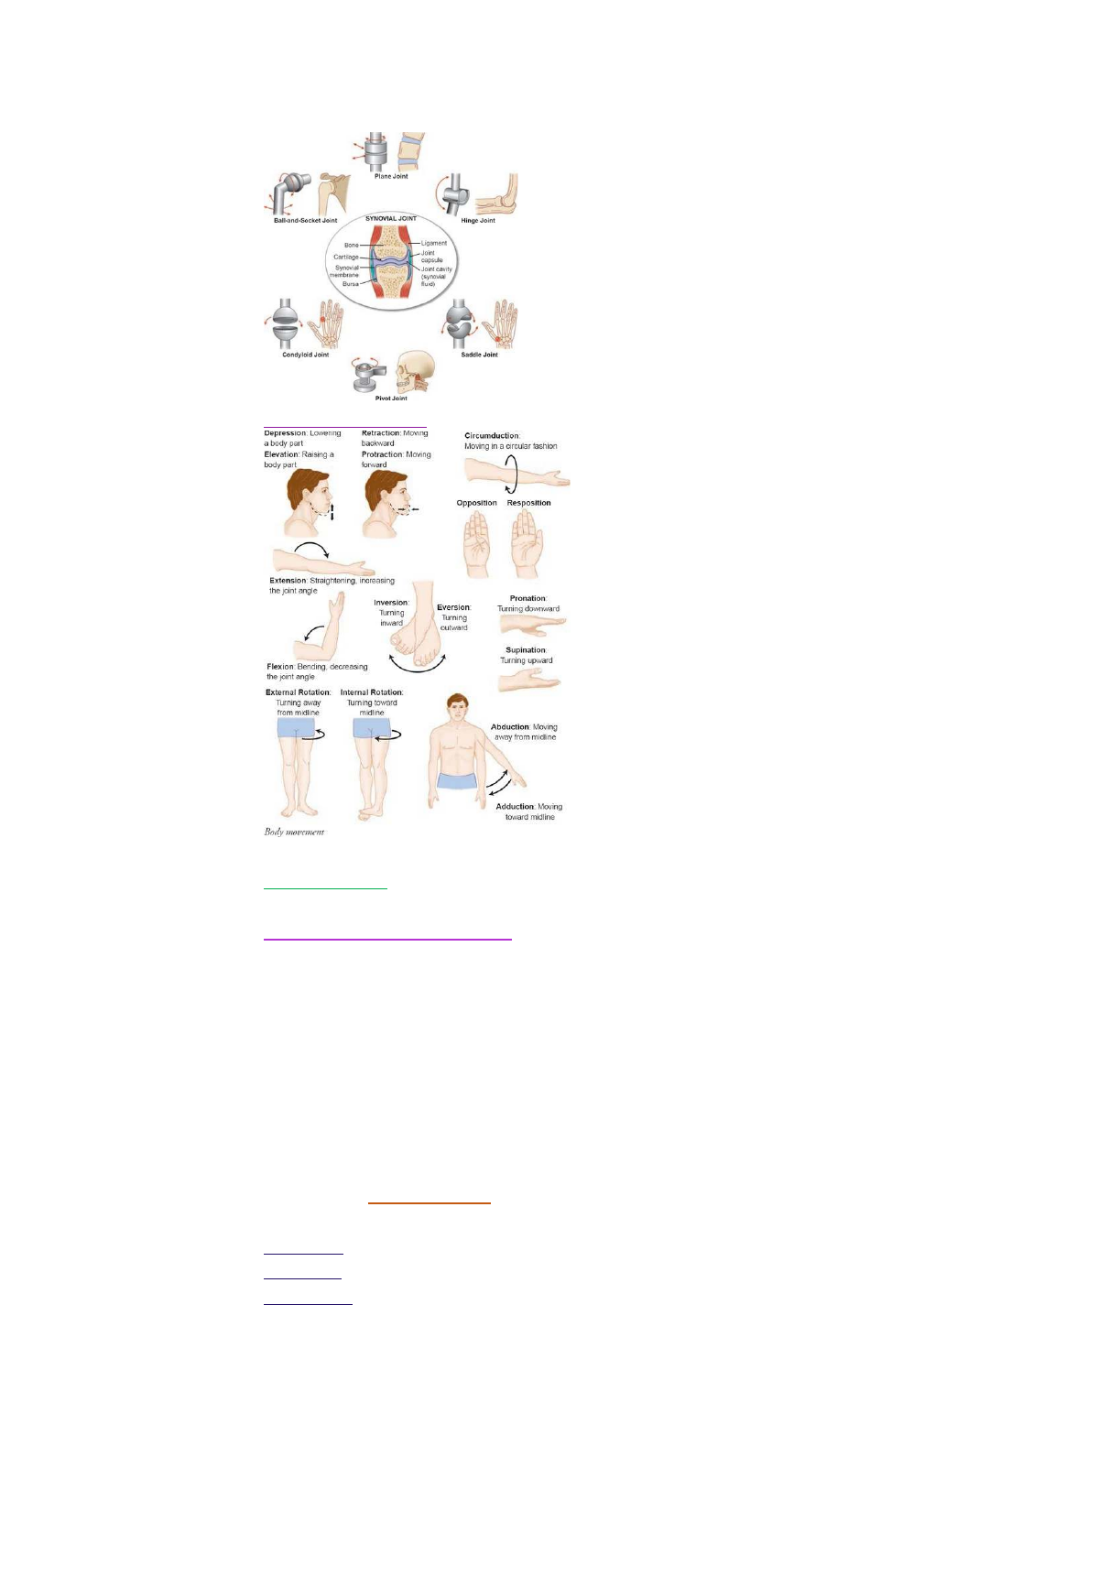
Body Movements:
2. What is osteoporosis?
Osteoporosis: A loss in bone mineral density that increases the risk of fracture
3. How do we document muscle strength?
Muscle Testing- Push/Pulls
oGrade 5- Full ROM against gravity and full resistance
oGrade 4- Full ROM against gravity and some resistance
oGrade 3- Full ROM against gravity
oGrade 2- Full ROM with gravity eliminated (passive motion) can't do
against gravity on
oGrade 1- Slight contraction when they push against you
oGrade 0- No contraction
Grade 3 through 0 is unexpected
4. What joint has the greatest mobility?
Synovial -- Ball in socket
5. What are unexpected findings in the spinal column?
Scoliosis - Curvature Lateral of the spine
Lordosis - Lower back coming inward (Curvature of lumbar spine)
Kyphosis- Hunch back (Curvature of thoracic spine)
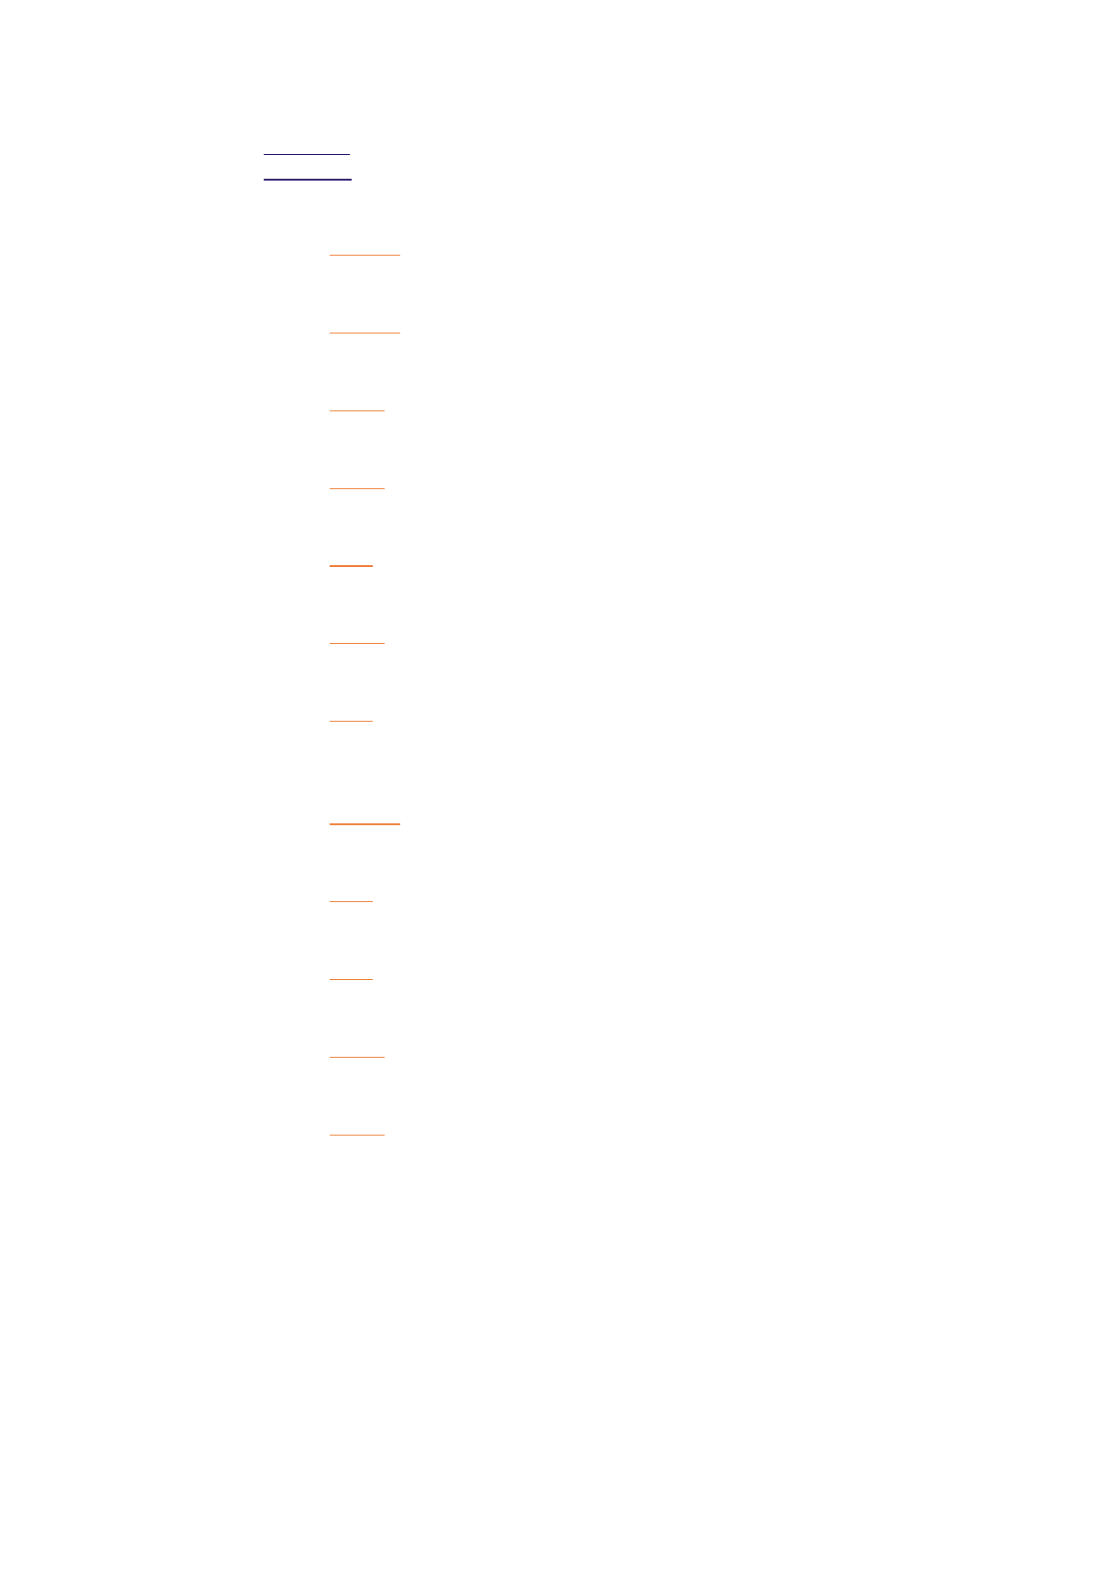
Flat back - No curve in back
Ankylosis - Fusing of a joint
6. Know the cranial nerves I-XII and how to assess them.
I – Olfactory: Smell
oSensory
Ask pt to close their eyes and see if they can smell the cotton ball
II – Optic: Vision
oSensory
Use Snellen chart to test for vision fields
III – Oculomotor: Eye movement
oMotor
Evaluate pt pupils with light
IV – Trochlear: Controls downward and inward eye movement
oMotor
Light, EOMs, PERRLA
V – Trigeminal: Biting / chewing, facial sensation
oBoth
Clench teeth, sensation on forehead check and chin
VI – Abducens: Controls parallel eye movement
oMotor
Light, EOMs, PERRLA
VII – Facial: Facial expression, taste
oBoth
Do different facial expressions, puff cheeks, raise eyebrows, close
eyes
VIII – Vestibulocochlear / Acoustic: Balance and hearing
oSensory
Check hearing, Weber tests (tuning fork)
IX – Glossopharyngeal: Tonge movement, swallowing, taste
oBoth
Gag reflex, taste
X – Vagus: Swallowing, speaking, cough, facial sensation
oBoth
Check uvula, sensation coming from skin to ear, swallow test
XI – Spinal Accessory: Controls strength of neck and shoulder muscles
oMotor
Shrugs shoulders against resistance, turn head laterally
XII – Hypoglossal: Tongue movement
oMotor
Tongue movement, stick out tongue
7. What are the signs and symptoms of a stroke?

8. How do we assess balance?
Romberg Test: Stand with eyes closed for 30 seconds
Heel to toe walk: (tandem walking)
9. What does the frontal lobe control?
Personality, intellect, expressive aphasia (knowing what to say, but can’t)
10. What does the hypothalamus control?
Temperature and sleep control bodily functions including release of hormones
from pituitary gland.
11. What is rheumatoid arthritis?
Rheumatoid Arthritis: Chronic inflammation affecting many joints.
oBody’s immune system attacks it’s own tissue and joints in body
What does it look like?
oUlnar deviation -- Fingers curve under
o
12. What is nystagmus? What cranial nerves are involved?
Nystagmus - shaking of the eyes
oCN III, IV, VI
13. What is accommodation in PERRLA? How do we assess it?
PERRLA:
oP- Pupils: Clear
oE – Equal: between 3 to 7 mm in diameter
oR - Round
oRL – Reactive: to Light both directly and consensually when you direct
light into one pupil and then the other
oA – Accommodation: of the pupils when they dilate to look at an object
far away and then converge and constrict to focus on a near object.
Extraocular Movement - cat whiskers
Ptosis - drooping eye lids (ABNORMAL)
Pseudoptosis: relaxation of the upper eyelid causing the lid to rest on the
eyelashes is an expected variation for an older adult client (NORMAL)
Exophthalmos - bulging eyes (relating to hyperthyroid)
Strabismus - eyes do not look in the same direction
Entropion - the bottom eyelid turns (in)
Extropian - the bottom eyelid turns (out)
14. What is the normal finding for pupil size?
Equal and between 3-7 mm in diameter
15. Know the levels of consciousness from alert to comatose.
Levels of consciousness
oAlert - spontaneous responsive and able to open eyes/answer questions
right away and correctly.
oLethargic- opens eyes but drowsy, responds but falls asleep readily
oObtunded- responds to light touch, confused, slow to respond
oStuporous - painful stimuli to arouse client (pen into nail bed). May not
verbally respond.
oComatose- no response to painful stimuli. Abnormal rigidity present.
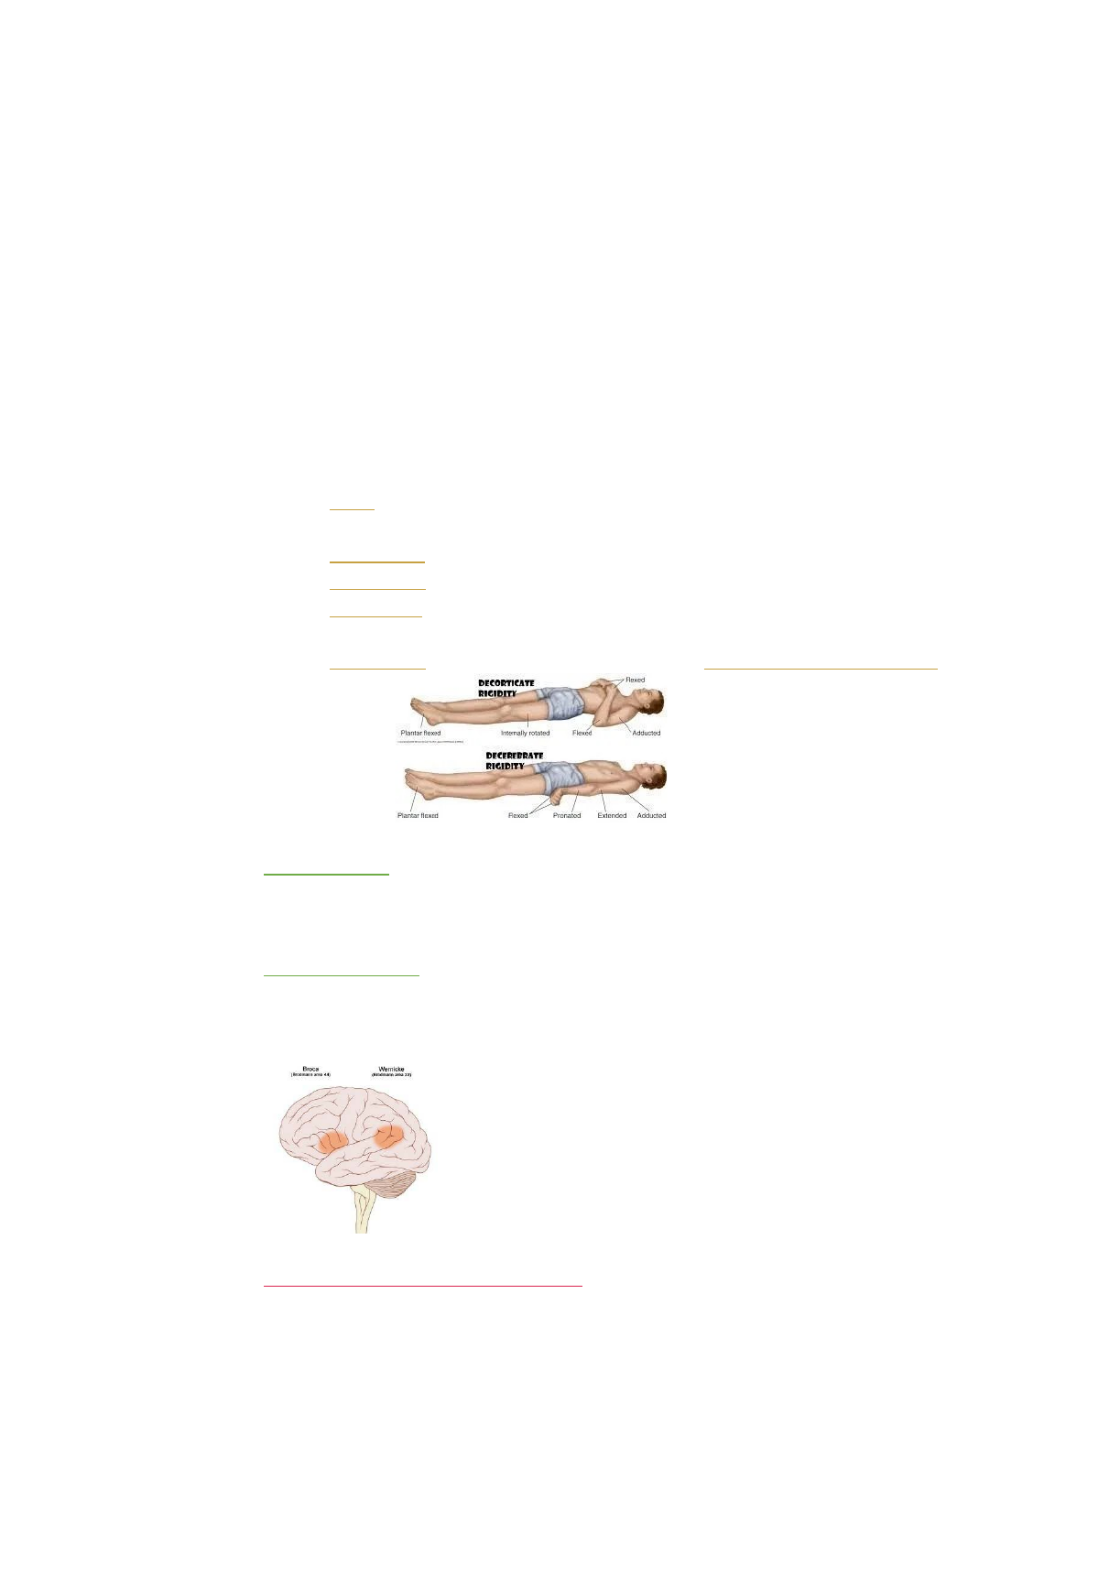
16. What is the Broca’s area? What is Wernicke’s area?
Broca’s Area: Region in the frontal lobe (dominant hemisphere) of the brain with
functions linked to speech production
Broca’s Aphasia or Dysphasia - Have extreme difficulty forming words and
sentences, may speak with difficulty or not at all
Wernicke’s Area: Region of the brain that contains motor neurons involved in the
comprehension of speech
Wernicke’s Aphasia or Receptive Aphasia - (jumbled, word salad)
oCan't understand words. Speak with regular rhythm / grammar
17. What is a GCS score?
Glasgow Coma Scale (GCS Score):
oEvaluates eye opening, motor responses, verbal responses

oHighest 15, lowest 3, NEVER 0, 1 across the board = comatose/no
reaction
Best score: 15
Comatose: 8 or less
Totally unresponsive 3
18. What is atrophy?
Atrophy: Decreases in muscle size due to disuse
Hypertrophy: Enlargement of muscle due to strengthening
19. What does it mean if your voice changes while swallowing?
Indicates aspiration
20. What are the expected findings for the deep tendon reflexes?
2 is expected on the 0-4 scale
o0 no response, 1 diminished, 2 expected, 3 above average, 4 clonus
Triceps Reflex: Extension of the elbow
Achilles Reflex: Plantar flexion of the foot
Bicep Reflex: Flexion of the elbow
Brachioradialis: Pronation of the forearm and flexion of the elbow
Patellar: Extension of the lower leg
Module 10 – Adult Health Assessment
1. What intervention can we take to reduce extraneous noise when auscultating lung
sounds?
Close the door, Skin contact, go underneath clothes, turn off noises in room – TV,
music, phone, Remove extra people in room – family
2. What is clubbing? Cyanosis? Signs of respiratory distress?
Clubbing: an angle of the nail greater than 160 degrees, and the nail and base can
eventually exceed 180 degrees.
o Can result from chronic low oxygen saturation, chronic or long-term
hypoxia
o
Cyanosis: bluish color
oLocation: Nail beds, lips mouth mucosa, skin, palms
oIndication: Hypoxia or impaired venous return
Signs of Respiratory Distress
o Possible breath sound heard
Stridor: crowing/animal sound
o Confusion
o Circumoral (around the mouth) cyanosis
o Use of accessory muscles, nasal flaring
o Neck vein distension
o Pale, diaphoretic
3. As a person ages, which orientation is first to go (person, place, or time)?
Orientation to time usually the first to be lost
4. Where do we take the patient’s posterior tibial pulse?
5. What area do we listen to each of the heart valves?
Aortic Valve: Just right of the sternum at the second ICS
Pulmonic Valve: Just left of the sternum at the second ICS
Erb’s Point: Just left of the sternum at the third ICS
Tricuspid Valve: Just left of the sternum at the fourth ICS
Apical/Mitral Valve: Left midclavicular line at the fifth ICS
Heart Sounds:
oS1 “Lub” -- Closing of the mitral and tricuspid valves
oS2: “Dub” -- Closing of the aortic and pulmonic valves
6. What is included in the general appearance?
Overall assessment of the pt.'s general appearance
oPhysical Appearance
oBody Structure
oMobility
oBehavior
oVital Signs
Module 11 – Breast & Lymph
1. What is the best time for a female to perform a breast self-examination?
4-7 days after the start of their menstrual cycle or right after menstruation
ends
2. How do we perform a breast self-examination?
Inspect -- Inspect breast for any changes
Palpate -- palpate lumps
o Should palpate each breast using pads of three middle fingers

Apply light, medium, and then form pressure to each area
o Beginning at outer edge near the axilla
Move across the breast tissue in a top to bottom fashion
o Palpate area in axilla
3. What are expected and unexpected findings?
Expected Findings:
obreast should be approximately the same size and shape with a smooth
contour
o Should be NO Dimpling, Rashes, Edema, Palpable lumps, Localized areas
of tenderness in the breast or axillae
oShould be no rash or drainage on the nipple or areola
Unexpected Findings: should notify provider if any changes in
o Breast tissue appearance or texture
oAbnormal findings
Significant breast size differences, Asymmetry of breast contour or
shape, Inflammation, Warmth, Localized tenderness, Changes in
skin texture or appearance, Lumps, Drainage
4. What is the purpose of the lymphatic system?
Lymphatic system: is a network of nodes, vessels, and organs that transport thin,
clear lymphatic fluid from the interstitial spaces in the body tissues to the blood
circulation
oLymph nodes: are small oval-shaped lymphatic glands arranged in chain-
like groupings along the lymphatic vessels
Lymphatic System three main functions
oDetecting and eliminating microorganisms
Such as bacteria, and viruses from the body
oAbsorbing lipids from the small intestines during digestion
oReabsorbing fluid from interstitial tissues
5. What is lymphedema?
Lymphedema: Who has a history of mastectomy may have this
o Due to the surgical procedure disrupting the normal pathways of lymph
drainage from the breast area
oEdema in the axillae or arm can be related to an infection in the breast,
arm or hand
6. What is the purpose of a mammogram?
A is to screen breast cancer mammogram
oX-ray picture of the breast
Mammogram screening every 1 to 2 years for females aged 45 and
above who have a low risk of breast cancer

40 if present in immediate family
Continue screening till 75 or longer
7. Where would you take blood pressure on a patient who has double mastectomy?
DO NOT place a BP cuff on the same side as the site of a mastectomy
o Can be but need to have a big cuffplaced on thigh
8. What is Peau d’Orange? What does it look like?
Peau d’Orange: When the breast tissue resembles the skin of an orange
Looks like an orange
9. What are some signs and symptoms of breast cancer?
Thickened rough skin
Edema
Inflammation
Unilateral rash
Peau d’Orange
Significant difference in breast sizes
10. Where is the tail of Spence located?
Breast are located over the anterior pectoralis muscle on the chest wall
Each breast is divided into quadrants:
oUpper outer
oLower outer
oUpper inner
oLower inner
In females an additional triangular area of breast tissue called the Tail Of Spence,
extends up and into the axillae lateral to the upper outer quadrant
11. What is a supernumerary nipple?
Supernumerary nipple: extra nipple
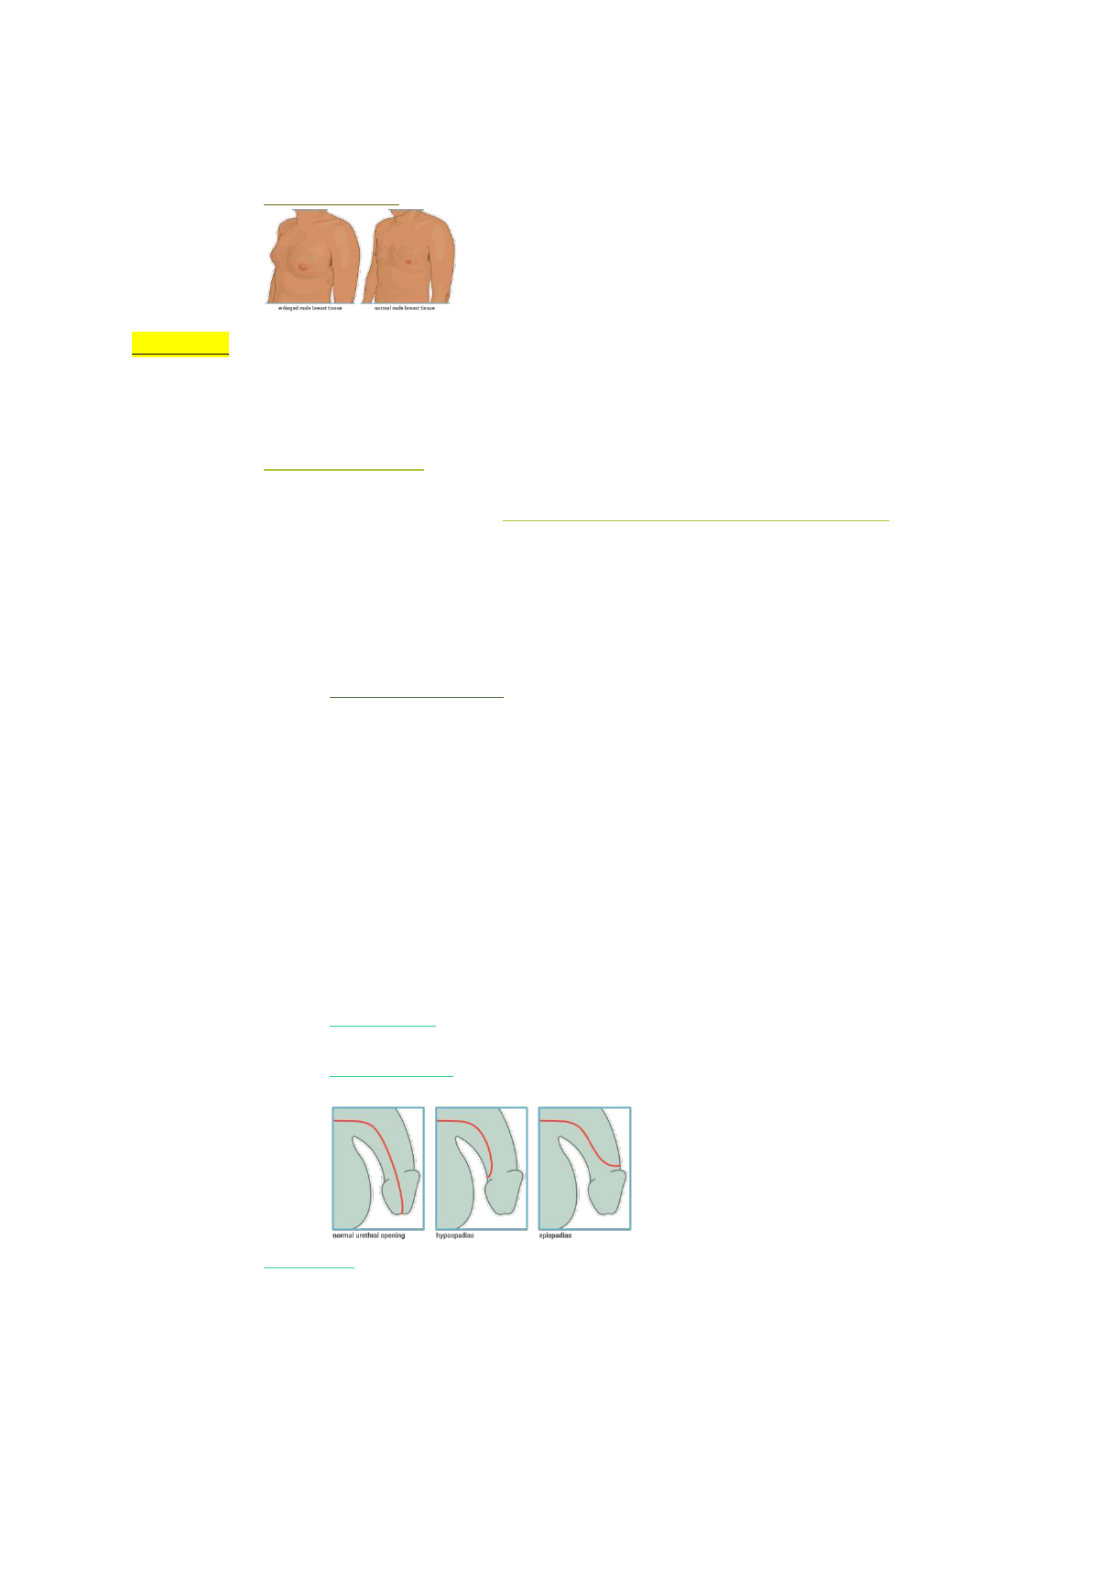
o Supernumerary = extra
12. What is gynecomastia?
Gynecomastia: enlargement of the male breast tissue
Module 12
1. When should a bladder scan be performed? How do we perform a bladder scan?
Should be performed when pt. reports
oAny problems with urinating, especially bladder distention
Bladder Scanner:
oWill measure the urinary volume within the bladder
o To measure Post-Void Bladder Residual Urine Volume, perform
the scan within 10 mins of pt. emptying their bladder
o Expected findings are post-void residual urine 50 to 100 mL
volume
Unexpected if greater than 100 mL notify provider
2. What location would the bladder be palpated?
If bladder distention is suspected the bladder will be palpable
oBladder distention: related to urine retention is caused by an inability to
empty the bladder during urination
o Could be related to obstruction, weak bladder muscles,
medications, or a neurological condition
oLocation -
oAbove the symphysis pubis along the midline of the abdomen
3. At what age should patients start getting screened for colorectal cancer?
Recommended for every pt. beginning at the age of 50
4. What is epispadias? Hypospadias? Phimosis? Priapism?
Unexpected findings in the urethral meatus
o Is the opening at the center of the glans (tip of the penis) for urine to exit
the penis is the urethral meatus
o Should be located midline in the center if the glans (Normal)
oEpispadias: Occurs when the meatus is located on the dorsal side of the
glans or penis shaft
oHypospadias: The meatus is located on the ventral side of the glans or
penis shaft
o
Phimosis: Condition in which the prepuce (foreskin) is not able to be retracted

Priapism: Painful, sustained erection without sexual desire that can last a long
period of time
5. What teaching should be done for a patient with genital herpes?
Genital Herpes: Groups of small painful fluid filled vesicles that break and
become superficial ulcers
oS/S in both male and female
o Small painful blisters on genitals
o Herpes (L), Warts (R)
6. What education should be provided to prevent HPV? STIs in general?
Genital Human Papillomavirus or Human Papilloma Virus = AKA HPV = most
common STI
o There is a vaccine
oSeries of 3 immunizations over a 6-month period
Sexually Transmitted Infections = STIs
o May be caused by bacteria, viruses, fungi, or parasites
oTo determine if someone has an STI you must obtain a culture, swab of
secretions from the genitals
oFor oral or anal sex culture of throat or rectum is obtained
oIncreased Risk for an STI:
o Unprotected sex
o More than one sexual partner
o Alcohol and drug use
o Sharing needles
o Nonadherence to the STI Tx regimen
7. What position should a woman be placed in for a vaginal examination? Perianal exam?
Position placed for a vaginal examination
o Lie in supine position with knees bent and feet placed on the bed
OR
o Can position pt. in a with their feet in stirrups lithotomy position
o Used more for performing an internal examination
o
Perianal Exam
o Usually placed in the Lithotomy Position
o Pt on their side with hip and knee bent will allow for visualization of
perianal area
o Sim’s Position?

o
8. What education should be done for a woman who is scheduled to have a PAP exam?
Papanicolaou (Pap) Smear Test
oAt least every 3 years while sexually active from age 21-65
o Screenings may cease if pt. Has a hysterectomy with removal of the cervix
OR is older than 65 years
9. What are some age-related changes for the perianal region?
Decreased control of the anal opening is an expected variation in older adults due
to weakened perineal muscles
Decline in estrogen or testosterone production
Enlarged prostate
Bladder problems
10. What can we do to promote urination for a patient who is having difficulty?
Maintain hydration (at least 2,000 mL/day unless restricted)
Provide perineal care
Teach bladder training
11. What condition can cause difficult urination in men?
Enlarged Prostate: Can obstruct the bladder outlet and cause urinary retention
and urgency which can lead to incontinence and UTIs
Benign Prostatic Hyperplasia
oAKA enlarged prostate
12. What education should be done for a patient who is preparing to have a PSA test done?
Prostate Specific Antigen (PSA)
oScreening for prostate cancer
oInstruct the patient to abstain from ejaculation for 2 days prior to
PSA blood test.
oShould be done starting at age 50 until 70, high risk start at 40 or 45.
13. What are hemorrhoids? What are the signs and symptoms?
External Hemorrhoids: Are dilated veins on the exposed portion of the anus
o S/S:
o Appear as tissue flaps that are painless. Irritated or thrombosed
(lack blood flow due to a blood clot)
Thrombosed Hemorrhoids: Appear bluish-purple, shiny, and full
o S/S:
o Local pain. Itchiness. Bleeding during BM
14. What is syphilis? Gonorrhea? What are the signs and symptoms? What do these look
like?
Syphilis: Caused by a bacterium that is transmitted from person to person by
direct contact with the syphilis sore
o Can be seen on
External genitalia, Vagina, Lips, Mouth, Anus, Rectum
oS/S

Chancre (painless, ulcer-like sore at site of contact)
Generalized Non itchy, painless rash
Sore throat
Low-grade fever
Aches and pains
Gonorrhea: Caused by a bacterium. Yellow/Green discharge
oS/S-
Dysuria
May be asymptomatic
Burning
o
15. When and how should males perform testicular examinations?
Once a month, While standing, After a warm shower
oGently roll each testicle between the fingers and thumb
16. What are the expected findings in a testicular examination?
Bumps on the skin of scrotum (could be from shaving). Ingrown hairs. Rash
Soft ropy cord, which is a normal part of the scrotum called the epididymis. Leads
upward from the top of the back part of each testicle.
17. What are the signs and symptoms of an upper GI bleed?
Tarry black stool
bright red blood in vomit
vomit that looks like coffee grounds
18. What causes post-menopausal vaginal dryness?
Decreased hormone levels after menopause cause atrophy and dryness of the
genitalia structures
oEstrogen Helps maintain the vagina’s lubrication, elasticity, and thickness
19. What are Bartholin’s glands?
Bartholin’s glands Surrounding the vaginal orifice are these glands
oThey secrete a lubricating mucus into the vaginal opening
Bartholin’s gland abscess – Unexpected finding
o It is a fluid-filled pocket with overlying red and shiny skin that is painful
and causes the labia to swell
o

