


The Role of Risk Management in Reducing
Loss Prevention
IEE 454 - Risk Management
Arizona State University-Tempe
December 15, 2024

Definition of the Problem
Introduction
Risk management (RM) has been defined as
the process of scheduling, classifying,
directing, and managing organizational
conduct in order to curtail the detrimental
effects of fortuitous losses at reasonable
costs on the organization.
Risk avoidance involves eliminating all losses
associated with a particular activity, loss
prevention involves reducing the chance of a
mishap occurring, and loss reduction
emphasize reducing the severity and impact
of losses once they occur. Loss prevention
techniques focus on reducing the frequency
of occurrences likely to result in claims
and/or lawsuits.
In health care, risk management has become
an important issue during the 1980s and
1990s. The complexity of the legal

environment has challenged institutions to
strengthen the practice of health care to
protect staff and hospitals from loss. Risk
management is defined as the “science for
identification, evaluation, and treatment
against the risk of financial loss. Risk
management also envisages the evaluation
and scrutiny of medical treatment to identify
and circumvent injuries to patients. It is
envisaged that in most cases of medical
malpractices, “In medical malpractice cases,
the duty owed by the defendant physician
arises from the physician-patient
relationship” (Shandell & Smith, 1990, p.1-
4).
What risk management is about?
RM is concerned with utilizing key functional
activities of the organization to reduce the
detrimental effects of accidental losses on
that organization at pre-judged and

predetermined costs. Further, the scope of
risk management can also be extended to
include aspects of recognizing, assessing,
and protecting against the risks of financial
losses that may arise due to risk
materialization.
Further, there have been paradigm shifts in
the underlying causes of fundamental issues
governing risks in patient management.
While at one time, the safeguards against
losses or damages to the financial strengths
of health care institutions and the
prevalence of a reliable treatment
environment were considered paramount,
this has now shifted in terms of greater need
for preventing harm and injury to patients by
offering them a greater degree of health care
protection and adequate safeguards against
injuries caused by neglect by concerned
health care professionals.

Thus, it can be seen that over time, the onus
has shifted from the health care
organization’s need to protect its health care
environment from outside malpractice
attacks to a more focused and perhaps
narrower need to keep the best health care
interests of the patient uppermost and to
improve the quality of service and discharge
all responsibilities vested upon the health
care workers, which, it is believed would
significantly reduce the occurrences of
medical malpractice and issues connected
therewith.
The industry’s risk manager of today faces
many new and exciting challenges. By
conventional practices, the job focuses on
safeguarding the pecuniary trust of the
organization and preserving a secure milieu.
Today, the focus has broadened to include
preventing patient injury and improving the
quality of service. The administrator and

physician must now respond and increase
the emphasis on a system that can monitor,
promote and guarantee the quality of
service. Their objective is to alleviate
malpractice judgments, cut defense
expenses, and manage the insurance
premium.
Background of the problem
The rising number of malpractice cases was
not being reduced through prompt and
speedy disposal of those cases by concerned
officials. The fundamental causes for these
issues to surface included issues arising out
of technology advancement in medicine,
which carried with it higher risks of injuries;
issues arising out of worsening relationships
between physicians and patients; and,
problems arising out of unrealistic demands
made by patients about modes of treatment
and their results.

The probability of medical errors increased
with the larger number of people involved in
inpatient care. Risk management is used to
secure the financial assets of an enterprise
against the risks of calamities by assuring
adequate economic protection and security
against perceived and imminent occurrences
of liability through appropriate risk cover
strategies, including insurance of property
and thus alleviating the possibility of
financial losses that may accrue.
The word ‘liability ‘is used in various ways,
but the general definition would be the state
of being exposed to damage, danger,
expenses, etc. The professional liability of
the hospital is an area of great risk and all
hospitals must decide on the amount of
coverage they will carry. Comprehensive loss
and exposure information must be collected
and the data analyzed before purchasing
insurance coverage. To ease the malpractice

crisis, state legislators enacted a variety of
laws designed to establish limits on the
number of awards, set up arbitration
screening panels, revised the contingency
fee systems, and modified the collateral
source rules.
Problem statement
Medical malpractice received a great deal of
attention in the early 1970s when a crisis
emerged due to the lack of availability of
liability insurance. Most insurance carriers
increased premiums at alarming rates, and
others stopped writing malpractice coverage
altogether, thereby shrinking market
capacity. The increased frequency and
severity of malpractice claims were the
primary factors precipitating these actions.
Insurers found themselves unable to
adequately predict the frequency of claims
or to adequately price this line of insurance.

Patients will have to bear the cost and
detriment caused by the lack of proper care
in the health care setting due to faults
caused by medical malpractice in health
care.
Purpose of the study
Purpose of study
The purpose of this study is to consider the
aspects of medical malpractices in a closed
environment of Wayne State University
Physician Group affiliated with the Detroit
Medical Center Hospitals in Detroit,
Michigan.
Research Questions
• Whether trusted methods are available
that could identify specific medical
outcomes of medical malpractices or
liability incurring thereon?

• What is the extent to which a risk
management program and risk managers
could make difference?
• Could gaps in physician-patient relations
impact medical malpractice?
• Could a collapse in communication in a
physician-patient relationship result in a
malpractice case?
• How could physicians avoid diagnostic
errors and lawsuits?
To prevent lawsuits against hospitals and to
prevent further injuries to the patient,
ensure compliance with state insurance
departments. Risk managers must develop a
close working relationship with the persons
who provide hands-on patient care. These
professionals are often the first to realize
that an untoward event has occurred. Risk
managers must establish an open line of
communication so that he or she is advised

of events as soon as possible. Risk managers
must develop an occurrence reporting
system that these professionals understand
and are willing to utilize.
Assumptions/Limitations
The study subject will be limited to Wayne
State University Physician Group (WSUPG)
affiliated with the Detroit Medical Center
Hospitals in Detroit, Michigan.
Definitions
Malpractice
Professional
liability
insurance
Unethical behavior during the course
of carrying out one’s official duties,
resulting in detriment, or inability to
provide the degree of care necessary
for the wellbeing of patients.
Insurance Coverage for liability arising
from the rendering of or failure to
render professional services

Risk financing
The science of evaluating all possible
elements of an institution’s financial
exposure utilizing prospective and
retrospective data and developing a
vehicle for investment or money
management that will allow for the
dollars needed in the future to pay for
the risk to be available.
Summary
Risk Management has become a growing
concern of all hospital administrators since
the 1970s. Whether the institution is profit-
motivated or not, it must be fully protected
from loss to remain competitive in the health
care industry. A program must be
established, personnel must be educated,
legal strategies must be planned, and
insurance protection must be ensured. The
goal is to provide quality service to the
patient and to avoid negligence. The hospital

should be a safe place for treatment and
improving health, not a hazardous
environment that creates further harm or
injury to the patient.
Literature Review
The industry’s risk manager of today faces
many new and exciting challenges.
According to custom, the work entails
maintenance of the financial stability of the
institution and upholding secure
surroundings. Today, the focus has
broadened to include preventing patient
injury and improving the quality of service.
The administrator and physician must now
respond and increase the emphasis on a
system that can monitor, promote and
guarantee the quality of service. Their goal is
to reduce malpractice verdicts, cut defense
costs, and control the insurance premium.

Some of the findings showed normal
circumstances within the study, but not all
injuries were due to negligence, and not all
injuries were preventable. Due to
deficiencies in prevailing systems, nearly
30% to 40% of mortality among stressed
patients could be due to avoidable issues in
medical attention, taking into account a
wrong diagnosis and delay in providing
treatment (Acute care, disability, and
rehabilitation, 2006, para.1).
These findings were based on the results of
studies concerning the incidence of injuries.
More findings prove that the severity of the
injury was more apt to be the determining
factor in deciding whether a claim would
arise. In conducted studies, it is seen that
early research is suggestive of the fact that
disabled people may not have the longevity
and inferior wellbeing as they become older
than people who have not been diagnosed

with any kind of physical or mental inabilities
(Acute care, disability, and rehabilitation,
2006, Priorities, para. 32).
The American Hospital Association (AHA)
gave guidance and it helped promote the
acceptance of risk management. Across the
country, hospitals are quietly improving the
way they provide health care services and
medical attention (Umbdenstock, 2009,
para.1).
Risk management entails the identification,
assessment, and taking of corrective
measures against threats and challenges
caused by fiscal indiscipline and, inter alia,
has issued directives to hospitals to enforce
risk management practices as a viable
solution for the impaired provision of health
services.
“All medical activities that can lead to injury
or death of any person, or damage to or loss

of property, material, or reputation must be
systematically managed regarding risk”
(Grose, 2005, para.1). This could be seen as
being within the scope of risk management.
Risk management also outlines the basic
elements of the program and directs that the
manager be someone whose training or
background was in hospital administration,
insurance, or safety engineering. This
guideline also stipulated essential
components necessary for an effective
program. This description listed mandatory
requirements but left space for modification
that would be dependent upon the unique
characteristics of the individual hospital.
“The steps of risk management are simple
and straightforward:
• Identify the risk
• Analyze and evaluate the risk
• Control or eliminate the risk

• Protect the agency and the consumers of
its services
• Manage any failures” (Risk management:
The steps of risk management, 2002,
para. 1).
In its simplest form, risk management in
health care has historically focused on
providing a safe environment for hospital
patients. With the formation of health care
systems in recent years, the scope of risk
management now expands beyond the
inpatient setting. Organizations have
affiliated components that provide not only
acute care hospitals but also the outpatient,
home care, and long-term care that patients
require.
The new structure of health care delivery
systems brings with it the obligation to
increase the scope of risk management.
“Thus, establishing expectations is a first

step in defining and delivering quality care
and services and minimizing risk in the
environment of long-term care” (Peterson,
2005, para. 1). Broadening the focus of
patient care is also a risk management
initiative. Research has emphasized the need
for recognizing that risk management now
means, the comprehension of the entire
gamut of care and devising ways and means
by which these could be improved. Normally,
patients may receive a range of care in
multiple settings from multiple providers of
care.
The continuum of care needs to be the
central theme of patient care, as paradigm
shifts occur, new policies are enforced or the
standards of care are upgraded and
refurbished to meet varying needs and
demands of patient care.

An effective risk management program
covers all aspects of hospital operations. To
achieve this goal, managers must establish
early warning systems, target clinical areas
or practices that present the greatest
exposure to liability, and implement
preventive action to minimize the risk
associated with these activities. “Several
professional regulatory agencies and other
industry associations have worked hard to
improve the quality of care provided in
nursing homes (now called nursing facilities),
the administration and governance of those
facilities, and in turn the reputation of the
overall field” (Pratt, 2009, p.73).
Risk management is primarily designed to
protect the financial assets of an
organization by assuring adequate financial
protection against potential liability through
appropriate insurance coverage, reducing
liability when untoward events occur, and

preventing those events that are most likely
to lead to liability.
The term ‘Liability’ may be defined in various
ways, but a general definition would be the
state of being exposed to damage, danger,
expenses, etc. The hospital’s professional
liability is an area of great risk and all
hospitals must decide on the amount of
coverage they will carry. Comprehensive loss
and exposure information must be collected
and the data analyzed before purchasing
insurance coverage.
First of all, it is necessary to analyze the gross
patient service volume, with relation to
inpatient and outpatient visits, and also
determine the number of employees on
staff, including full/part-time employees. It is
also necessary to review any case history of
previous losses and identify the number of
legal expenses paid therein. Evaluating loss

projections: this can be accomplished in
three steps.
1. Determine the frequency and
magnitude of the loss, the nature of the
injury sustained is the best predictor of
the value of a loss;
2. Adjust frequency averages to reflect
significant future changes in hospital’s
risk climate; and
3. Review the accuracy of loss payout
estimates.
This is to include the settlement amount and
the cost of the investigation, and defense for
both paid and reversed cases. A skilled
attorney should be retained for a second
opinion as to the estimates of case values.
No one can estimate the amount of coverage
an institution should carry, because each
case differs in each area of care. Larger
amounts of fund payouts are needed for

meeting lawsuits awarded in court
settlements. After the data has been
analyzed, a risk manager would prepare for
the future loss by purchasing insurance.
Most hospitals “overkill” the expected loss
projection and settle for the purchase of a
premium that protects against catastrophic
settlements and payoffs which are in the
millions. Insurance coverage is paid for
protection; the risk manager can further
protect the institution by ensuring all health
care providers work towards preventing loss
within the institution.
Risk managers are responsible for
developing systems to prevent injuries and
other losses within the organization.
Performance improvement actions are often
initiated in response to suggestions offered
by the risk manager. Education is also an
invaluable tool in risk management and
sometimes is the only activity required to

prevent potential safety problems. “Patient
care and accessibility to mental health
services rest not only on clinical skills, but on
a place to practice them and an organized
system supported by staff, physical facilities
and funding” (Reid, D J., & Reid, W H., 2009,
Abstract, para. 1). Risk managers in many
healthcare organizations are responsible for
developing policies and procedures aimed at
preventing accidents and injuries and
reducing the organization’s risk exposure
(Johns, 2002).
The specific policies and procedures that
constitute a risk management program in a
hospital are developed in collaboration with
the hospital’s legal counsel. Judicial
interpretation of statutory law in the court
system is a continually evolving process and
hospital leadership and governance are well-
advised to seek the advice of counsel to
ensure that risk management practices

adequately protect the organization.
Generally speaking, the infrastructure of a
risk management program is designed to
circumvent, or alleviate monetary setbacks,
allocate funds for compensation and/or
damages, and also clear the corporate image
impediments caused by legal claims and
lawsuits.
Prevention is a critical aspect of any effective
risk-management program. Staff members
need to be provided with the right kind of
training and exposure to deal with
emergencies, which may not be the result of
their actions.
In summary, risk management has become a
growing concern of all hospital
administrators since the 1970s. Whether the
institution is profit-motivated or not, it must
be protected from loss to remain
competitive in the health care industry. A

program must be established, personnel
must be educated, legal strategies must be
planned, and insurance protection must be
ensured. The goal is to provide quality
service to the patient and to avoid negligent
acts. The hospital should be a safe place, not
a hazardous environment that creates
further negligence.
Sentinel Event Statistics
This part of the study shall examine events
that have a high capacity for attracting
liability or cause for damages that result in
lawsuits. It shall also consider ways and
means by which these incidents could be
prevented. According to the cases reviewed
by the Joint Commission of Sentinel Event
National Statistics as of June 30, 2009, there
could be many kinds of surgical errors or
delays that could harm, or cause death to
patients, and thus give rise to criminal or civil

proceedings for medical wrongdoing. High
on their lists are wrong-site surgeries
(13.4%), suicides (12%), operative and post-
operative complications (11.1%), and delay
in treatment (8%). (Appendix 1 and 2)
It would be presumptuous to blame for all
kinds of errors on health care providers.
However, errors caused while transfusing
fluids, errors while administering injections
and anesthesia, deaths caused by ventilator
malfunctions, etc., do come within the
purview of due services to be rendered by
health care providers. Thus, they would be
liable for potential legal action, at the choice
of the aggrieved patient or their families.
The authors took up an empirical study on
the aspects of care of patients undergoing
treatment in three sections of a large urban
teaching hospital. Of the total 1,047 patients
being considered, 185, representing 18%

had, at least one serious unfavorable
consequence. The rate of such unfavorable
consequences increased with the patient’s
length of stay. There is a 6% probability of
adverse effects increasing with every day the
patients stay in the hospital. The highest
incidence of mistakes (28%) occurred during
the surgical intervention and daily care.
During surgery, it was 10%, and intensive
care patients were most likely to have critical
impediments caused by medical errors
(Annotated resources: Sentinel events, 2009,
para. 3).
It is anticipated that there will be an increase
in the findings of medical negligence against
physicians as a result of the change in
standards for the evaluation of medical
negligence” (Medical professional liability
insurance trends in Asia; Malaysia, n.d., p.3).

The increase in such cases is a cause for
major concern since these incidents could
trigger off suits of medical malpractices,
especially if large-scale death or injury is
involved.
Omissions and delays
In a typical medical malpractice case, the
onus would be on whether the mistake(s)
made by the nurse “amounted to deviation
from standard care” and caused harm and
detriment to the patient, or direct cause of
death to the patient (White & Traux, 2007,
p.63). In the event, the nurse was employed
by doctors as an agent, or member of the
group, these doctors or groups would also be
legally held responsible for the injuries
caused to the patient.
Utilization Management and Risk
Management

Utilization Management (UM) may need to
be integrated with Risk Management (RM)
so that coverage of aspects such as,
insurance reimbursement billing and
hospital stays (typically UM functions) work
in harmony with patient omissions and
delays in treatment, medical malpractices,
and its aftermath (typically RM functions). It
is believed that in most scenarios,
importance to RM may not be possible,
mainly due to staff shortages, and also due
to the non-critical character of its activities;
thus, RM and UM must work together, to
enhance the quality of treatment, eliminate
or significantly reduce aspects of medical
malpractice and so on.
Medical Malpractices Jury Trial Verdicts
However, it was also seen that of the medical
malpractice verdicts by jury considered
during the calendar year 2008, of the total of

nine verdicts, eight have gone in favor of the
defendants, and only one has gone in favor
of the plaintiff, or the aggrieved party. This
was a case involving misdiagnosis, which was
settled for an amount of $2,200,000
(Medical malpractice jury trial verdicts
(January 1, 2008- December 31, 2008, n.d.).
Next, it is necessary to consider the
benchmarks that need to be achieved under
the Operational Risk Management & Safety
Assessment (ORM&SA), laid down by Wells
Fargo Healthcare Group. The modus
operandi for conducting such assessment
would be in terms of assessing present
compliances and how deficiencies in the
present system to make it congruent with
desired levels could be achieved. The
assessment would also include compliance
audits and in-depth questionnaire-aided
assessments in major functional areas of
health care.

Enterprise Risk Management
Again, Enterprise Risk Management (ERM)
forms a major area of public and
governmental accountability, including in its
scope, management of emergency room,
infection control, laboratory, blood bank,
and transfusion controls. Again, critical areas
where risks of medical malpractices could be
high are obstetrics, radiology,
anesthesiology, and oncology, and pain
management. This is more sharply
accentuated in geriatrics and post and pre-
natal interventions.
According to the Wells Fargo Healthcare
group, a detailed and comprehensive view of
all medical and patient-related aspects of
patient care must be made. According to
them, “The purpose of this Operational Risk
Management & Safety Assessment (ORM &
SA) is to assist an organization in determining

how prepared it is to retain risk as well as
determine if the care that is provided to the
patient meets established standards of care
and other recognized benchmarks” (Wells
Fargo Healthcare, n.d.).
Aspects that influence quantum of coverage
Many aspects need to be considered while
taking up the question of medical
malpractice in the hospital setting. For one
thing, hospital administration needs to
decide upon the amount of coverage that it
needs to carry and this has to be laid out on
a scientific and deterministic basis. For
another, the coverage would depend upon
several variables, which may depend upon
controllable and uncontrollable factors. The
major aspects that need to be covered would
be gross patients and their service volume,
including a breakdown of inpatient and
outpatient statistics. It is also necessary to

find out the number of employees, including
health care professionals whose conduct
could have an impact and make it subject to
risks of medical malpractices.
Legal history could dictate future trends
It is evident that before a risk management
program is set into place, the history of
medical risks and their settlement in the
context of the institution needs to be
identified and assessed. It is necessary to
know cases of previous litigation regarding
medical malpractices that have been
instituted either against the institution or
against any of its constituent practitioners. If
so, it is also important to know how these
issues were dealt with and the extent, or
amount of damages that were made by the
institution, or its represented insurance
agencies, or firms. This aspect is important
since this would bring out the public image

that is associated with this particular health
care center.
Importance of public image in health care
settings
It is common knowledge that, to a very large
extent, the survival and growth of public
health care institutions depend largely upon
the public image and goodwill that it has
earned over years of providing health care
services to patients. However, even a few
instances of medical malpractices by its
constituted agents, or health care providers
would be enough to earn disrepute, which
could significantly impact its image and
potential prospects, since few patients
would be willing to visit health institutions
where the medical services are
compromised or neglected, inviting legal
complaints and actions.

Thus, many factors impinge upon the aspect
of medical malpractices, which cannot be
seen in isolation but has to be seen in the
context of the individual case studies. The
importance of a proper methodology for
seeking out how best these issues could be
addressed would form the next part of this
paper.
According to the practicing physicians at
Wayne State University Physician Group
(WSUPG), the responsibility for controlling
medical malpractices vests with the
profession itself (Prognosis E-New: Fieger,
Howard debate merit of health courts,
2005). According to the physicians, there are
reasons to believe that health courts could
be the best place where medical malpractice
issues could be sorted out.
The judges have well acquainted with
Medical Malpractice (MM) laws and with the

help of unbiased observers, the judgments
for such cases would be reasonable and in
the best industry practices. Besides, the fact
that WSUPG sets high professional standards
of medical practices could lower the rates of
such malpractices and move toward a more
transparent and patient-oriented system of
care provision.
Data Analysis
Introduction
Since January 1989, the Joint Commission on
Accreditation of Health care Organizations
(JCAHO), an autonomous agency that
assesses and evaluates the performance of
Health Care institutions and programs in the
length and breadth of the USA, has
enunciated benchmarks for patient safety.
Although JCAHO benchmarks are not key
drivers in risk management, nevertheless,
there is evidence to prove that these ethical

and commercial elements are critical to any
strategic planning models concerning risk
management. Through this, JCAHO provides
an excellent vehicle for creating a culture of
patient safety and welfare.
The goal of risk management is to reduce an
entity’s accidental loss of corporate assets,
personnel, revenue, and reputation. Each
organization’s risk management plan should
include the following components: the plan’s
objectives, key elements, responsibilities,
methods, and areas of focus for the current
year.
Risk Management Plan
• Objectives: The main aim of the internal
regional medical monitoring unit is to
supervise risks to reduce losses, protect
resources and assets and also ensure
security, safety, and stability of condition
of staff members, care providers,

patients, and visitors. This could be in
terms of a separate unit that has been
given the responsibility of taking care of
the above-mentioned aspects, thus
allowing other care-providing units and
departments to carry out their normal
routine functions.
• Key Elements: Risk management involves
several key elements. The methods for
implementing these elements are
described later in this document. The key
elements are identifications of risk
issues, evaluation of areas of risk,
communication of risk information,
education of organizational personnel
and others, and reduction of risk.
• Responsibilities: The risk manager will be
responsible for managing risk
management activities.
These activities include:

1. 1. Coordinating insurance coverage.
2. Managing claims against the facility.
3. Interfacing with legal counsel.
4. Identifying and analyzing areas of risk
exposure.
5. Considering and proposing suitable
peril management practices.
6. Mounting and upholding an
information supervision scheme.
7. Executing and observing security,
teaching, and quality assertion agenda.
8. Inspecting, detailing, and observing
risk management data and information.
Although the risk manager has the
responsibility for this plan, risk cannot be
reduced without education and participation
by all team members. All team members are
expected to report events, follow standards
of practice, identify risk events, guide the

organizational mission, implement systems
to reduce risks, and budget monies to solve
problems. Risk managers will be available to
consult with any department or manager to
assist in a risk assessment of the
environment or system. Risk managers will
also research issues and gather additional
data to assist decision-makers in the search
for solutions. This research may include
local, state, or national data.
Methods for Carrying Out Key Elements
Identification
The methods of identification include, and
are limited to, incident reports, medical
device reports, customer comment tracking
forms, attorneys’ health records requests,
security reports, performance improvement
referrals, medical staff/peer review reports.
Safety hazard reports, supervisor reports,
documentation by staff and/or phone

conversations with individuals who feel a
need to speak about issues, and visual
inspection of all areas of the organization to
identify potential risk situations.
Committee membership and participation
are essential for risk identification. Risk
managers will assist in the credentialing
process whenever there is a request or need
to do so. Risk managers will research the
appropriate databases and assist in
obtaining profiles concerning procedures as
needed or required by the medical staff
bylaws. The aspect of Risk Management next
needs to be seen in the context of an
illustration, or example, that considers an
internal structure within the health care
setting called Regional Medical Center
(RMC). In the case of Wayne State University
Group (WSUPG), it may be the Detroit
Medical Center.

There have been many issues that arise due
to a lack of communication and
understanding between health care
providers. “Despite the complex issues we
face as academic and clinical partners,
WSUPG and the Detroit Medical Center
share a common mission “(Wayne State
University and Detroit Medical Center settle
a dispute over compensation for physician
services, 2009, para. 7).
Risk management will identify high-risk
areas due to trends in practice, advanced
changes in technology, and national data
that might highlight potential areas of risk.
The high-risk areas are the emergency
department, obstetrics, surgery, anesthesia,
critical care, and pediatrics. These areas have
the potential for creating situations that can
have a significant economic and emotional
impact on the organization. Risk
management will monitor the off-campus

sites by receiving notification of any
incidents that occur off-campus, as well as
through periodic visits by the risk manager to
each site. Maintaining information is and
always will be the foundation of risk
management. Most information will be
maintained on the computer system for ease
of data retrieval, to keep paper to a
minimum, and to make record transfers
easier and timely.
Regulatory agencies are constantly changing
guidelines, regulations, and statutes. The risk
manager will monitor changing regulations
and assist team members in implementing
practice changes pertinent to the
regulations. Agencies that may affect the
organization are JCAHO, The Centers for
Medicare and Medicaid Services (CMS), state
licensing boards, state and federal legislative
bodies, and others.

Evaluation
A major role of the risk management
department is to continuously evaluate data,
systems, processes, events, documents, and
departments or areas for risk. This can be
done through committee participation,
reporting mechanisms, such as patient
satisfaction, data and incident reports, data
trends such as needle sticks, and reported
medication errors.
The risk management department will
complete an investigation of any occurrence
and rate the risk of the event. A further
investigation will then occur, with priority
given to all events that alter an outcome for
a patient, a staff member, or a practitioner.
The method of investigation will be
determined by the event itself but could
include data collection and review. Medical
record review, committee participation,

incident report investigation, making rounds
in the area, consulting with specialists to
assist in the investigation, including other
managers, educators, insurance carriers
attorneys, law enforcement and finally the
process such as root- cause analysis, case
study, or peer review to determine what
occurred.
The leadership staff in the organization will
then be responsible for changing processes
or improving systems to reduce future
occurrences and risk. Risk analysis will also
be reported periodically to the board of
directors for its overall direction. The risk
management department will maintain
confidential records of the analysis, including
the process taken to evaluate processes that
may be causing increased risks and the
suggested actions for improvement. After
the analysis is completed, the action steps
will be implemented to solve problems or to

improve the outcome for the parties
involved. After changes have been made, a
periodic evaluation of the success of the
change will occur, and the evaluation will be
reported to senior leadership.
Communication
Communication of risk management
functions, information, data collection, and
risk assessment is an important function
within the risk management plan. The
priority for communication is to inform and
educate employees, physicians, customers,
and others of risk issues and problem-solving
processes. Confidential information will be
shared only on a need-to-know basis without
exception.
Risk management will determine the
confidentiality of certain communication
links for direct and discrete information.
Communication may be directed to any or all

of the following groups, as deemed
appropriate: administration, medical staff,
employees, patients, the board of directors,
and employees. Communication to the
board of directors will be done every
quarter. This communication mechanism will
also include performance improvement
activities related to the risk management
plan.
Education
Education regarding risk management
activities, risk reduction, opportunities, and
other ways to improve the organization is a
key element of the risk management plan.
The medical center will also participate in
collaboration with the parent organization’s
national risk management program through
involvement in the Risk Management
Incentive Program. Proven measures of risk

reduction may result in lowered liability
rates.
The measures may be in the form of general
orientation, root-cause analysis sessions,
special education programs, conferences,
medical staff meetings, employee staff
meetings, board reports, department
rounds, and informal discussions. Risk
management will be prepared to assist the
organization in national regulatory changes
that influence how the work is done.
Educational opportunities will be sought out
in the employee environment to reinforce
the principles of risk reduction.
Reduction
The outcome of any effective risk
management plan is to reduce risk. The
problem-solving process of identification,
evaluation, education, and communication
will be the mechanism for reducing risk. The

reduction of risk will provide a safer
environment for patients, staff, providers,
and visitors. Each of the activities will
identify action steps and personnel required
to resolve issues. Problem-solving activities
and their outcomes will be shared through
Areas of Focus in Fiscal Year 2008:
1. Timely incident reporting
2. Reduction of medication errors
3. Implementation of workplace
violence program
4. Data trending of resuscitation
outcomes
Attention to medical errors escalated over
five years ago with the release of the study
from the Institute of Medicine (IOM), To Err
is Human, which found that between 44,000
and 98,000 Americans die each year in U.S.
hospitals due to preventable medical errors.
By far, mistakes in hospital settings list in the

fifth and eighth spot as the main causes of
fatality, accounting for deaths of most
Americans when compared to breast cancer,
road accidents, or AIDS.
Nearly five to ten percent of patients put into
hospital settings are affected by major errors
in treatment. These numbers may
understate the problem because they do not
include preventable deaths due to medical
treatments outside hospitals (Kaiser, 2007).
If deaths due to medical treatment outside
hospitals are considered, the figures may be
larger. Most often, medication errors can be
attributed to one or more of the following:
• Faulty prescribing, monitoring, or
refilling practices
• Inappropriate formulas
• Improper documentation
• Inadequate communication

How can physicians avoid diagnostic errors?
Expert physicians have to
investigate/document all patient complaints
and maintain a comprehensive record of the
patient’s history by implementing a template
to ensure consistency and thorough
evaluation and documentation. Physicians
should avoid allowing age to become a
determining factor in the evaluation of a
diagnosis. Review results from a previous
diagnostic exam and promptly pursue
further diagnostic studies. Also, ensure that
a diagnostic tracking system identifies
delinquent follow-up. Handwriting should be
legible and easy to understand. Legibility
issues are resolved through the use of
electronic prescription ordering and record
keeping.
The use of preprinted prescriptions for
frequently prescribed compounds is another

effective method of providing easily read
prescriptions and avoiding illegible orders.
Physicians should avoid verbal orders. If
verbal orders must be given, physicians
should repeat the order, spell the name of
the medication, and ask for the order to be
repeated to verify understanding.
Alternatively, consider the use of fax
transmission of prescriptions to the
pharmacy to provide a written document
that can be maintained in the patient’s chart
(JACHO, 2005).
What are the risk exposures and hazards?
Clinical judgment is a risk exposure for
physicians. Many factors underpin a general,
or specific lack of data needed to reinforce a
physician’s clinical diagnosis about patient
care. They may include, among others, a
partial or mistaken history, excess
dependence on referring physician’s

diagnosis without independent evaluation,
inability to get a consultation,
misinterpretation of diagnostic studies,
insufficient office systems to monitor test
results, cognitive prejudice, inadequate
supervision of personnel and scarce
knowledge.
How can corrective actions be
implemented?
To enhance the security aspects for patients
and disallow mistakes, the Government
should set up a National compulsory
unfavorable occasion reporting system so
that health care settings disseminate
information that can assist them in
correcting wrong systems and procedures.
Computer prescriptions could significantly
reduce errors in dispensing drugs and
medicines.

This would assist doctors in dealing with
issues arising out of indecipherable
handwriting and by routinely examining for
mistakes or unsuitable drug usage.
Despite a ruling by the Institute of Medicine
in 2006 that preventable medication error
costs $3.58 billion annually, just 5% of
hospitals have taken concrete steps to check
such occurrences. Health care settings could
also help by evolving systems that could
control workweeks of professionals to
diminish errors arising out of tiredness and a
need for rest.
The Institute of Medicine (IOM) report called
for a 50 percent reduction in medical errors
by 2004. Unfortunately, it is not possible to
quantify the number of errors today, and
therefore, impossible to determine if the
goal has been met. The number of errors
remains high and there are many issues

around substandard quality in addition to
error. The 1999 IOM report focused
primarily on errors in hospitals, but errors
occur in other settings, such as ambulatory
care and nursing homes (Bleich, 2005).
Quite often, avoidable errors may occur due
to mistakes in recommending drug intakes or
consumption of drugs. Eliminating
medication errors need to be seen in the
light of a national agenda for alleviating
medication errors premised on statistical
data regarding the regularity and economic
costs of such errors and proof of the
effectiveness of a range of preventive tools
(Preventing medication errors: Quality
chasm series, 2009, para.1).
Hospitals and other health care
organizations decrease medical errors by
using expertise, improving processes,
identifying mistakes that cause damage, and

building a customs of security. Empirical
studies have shown that Computerized
Physician Order Entry (CPOE) helps obviate
medication errors. It involves entering drug
orders directly into a computer system
rather than on paper or orally (Vantage
Professional Education, 2006). It is believed
that the use of computer software for
generating physicians’ orders is useful in
alleviating mistakes arising out of medical
errors or misrepresentations.
Various conducted studies have reinforced
the need for greater use of computerized
patient order entry (CPOE) which obviates
ambiguity in handwriting, decimal points, or
acronyms. All matters are processed digitally
under this system, thereby dramatically
reducing the chances for manual errors and
difficulties in deciphering the handwriting of
health care professionals.

Today, most Americans don’t believe the
nation’s quality of care has improved. As a
result, “as studies continue to point out the
high rate of medical errors and their
devastating effect on millions of citizens,
many groups are making an effort to get
patients more involved in protecting
themselves” (News: New online brochure
hopes to get patients more involved in
protecting themselves, 2005). The
probability of occurrence of various kinds of
medical errors is immense. Thus, the main
objective is in reducing the number of
possible medical errors in various types of
health care centers. Much work remains to
be done and there is still much to be learned
but the important issue is that systems,
process improvements, and
recommendations are now being set into
place (Vantage Professional Education,
2006).

Doctors being human, the public needs to
empathize with them for errors that could be
made. But it is well within their command to
reduce such errors to minimal levels. Firstly,
a new technology that could significantly
alleviate the probability of errors needs to be
evidenced. However, till such time such
errors are sought out and permanently
decreased, these would continue to be the
main areas of medical care.
Summary and Conclusion
Summary
The purpose of this future research is to
determine ways to create a safer patient
environment and awareness of safety
practices among employees. Physicians play
a vital role in reducing the prevalence of
medical errors. Physicians should provide
leadership to make patient safety a priority

and to increase staff awareness of potential
patient safety threats.
The problem statement dealt with the high
cost of malpractice insurance premiums.
Since the 90’s the nation’s health care bill
has added $7 billion to the cost. The
information received from the Institute of
Medicine stated that by 2010 there should
be a 50% reduction in medication errors. The
continuation of committee reviews,
implementing policy and procedures, checks
and balances, education, and effective
communication can avoid diagnostic errors.
To achieve these goals, much work lies
ahead.
For this future online survey questionnaires
and interviews would be conducted with
several respondents chosen specifically for
this purpose. They formed an unbiased
cross-section of health care professionals,

members of the nursing community,
physiotherapists, and other therapists who
were involved in the process of health care
delivery.
The underlying factor is that the best
interests of the patient need to be always
considered and needs to be benchmarked
against the best industry practices both in
terms of a measure of care and the risk
management commitments and
responsibilities that are taken in group and
individual settings. Insurance companies and
underwriters also play major roles in
assessing health care insurance and its
settlements due to accident or medical
malpractices.
Where conflicts arise in the context of the
delivery of health care, especially sharing of
patient responsibility, medication, and such
other issues, the underlining factor should

be whether these issues are capable of
causing detriment to the health and welfare
of the patients and lowering the degree of
care. If so, it needs to be eschewed and
patient care programs need to be enforced.
There is a need for trusted methods to be
developed and enforced that could consider
the impact of medical malpractices in the
present state, and ways and means need to
be developed that could enhance patient
service and care, both in qualitative and
quantitative terms. There is a need for
utmost trust and confidence to be exercised
from both sides, to foster an environment of
risk management and its smooth and
effective transition into the administrative
health care functioning of care centers.
In the event risk management is not given
due importance, even a single incident of
medical malpractice could considerably

impinge upon the financial viability,
goodwill, and prospects of health care
institutions. The depletion of financial assets
by way of damages and penalties, indulging
in litigation aside, would have far-reaching
implications on the authenticity and
reputation of the institution.
Moreover, it could also compromise on the
faith and reliance placed by patients and
their careers, insurance companies,
underwriters, and a host of other
intermediaries and firms that do business
with such institutions. Thus, it is very
important and intrinsic that health care
institutions, however small they may be,
need to have a robust and pro-active risk
management system in place, not only to
safeguard the assets of the institution from
being frittered away in long and expensive
legal cases but more significantly, to protect
the best interests of the customers, clients,

and patients who are depending upon them
in more ways than one.
The outcome of the deliberations with risk
manager respondents may also reinforce the
fact that a two-way communicating system
between provider and patient is very
important, and underpins the degree of trust
and confidence each places on the other for
the safe delivery of services and the right
attitude to getting well.
Conclusions
This future research would focus on ways
and means by which patient health could be
made a number one priority and aspects of
risk management in health care be closely
monitored through the implementation of
regular control mechanisms designed to
keep events of risks at the barest minimum.
The survey being an ongoing process that
needs to consider contemporary health

settings and characteristics at the time of the
research program, it has been well-advised
to be taken up during the time of future
research for achieving the most accurate
results.
The main aspects that advanced and
improved health care assume in the present
context is in devising ways and means and
strategic decision making which envisages a
heightened sense of comfort and health
assurance for patients and also enhancing
their standards of safety and security in
terms of lesser susceptibility to injuries,
greater comfort zones and ensuring the
overall high standards of providing care that
would not only ensure congenial patient
treatment atmosphere but also afford them
the desired degree of care which they are
entitled to.

While individual strategies and health
enforcement policies and practices vary
from one health care institution to another,
the fact remains that there are important
broad-based guidelines that need to be
adhered to, if a genuine improvement in the
current health care standards is desired.
This included the clear judgment of the
qualitative and quantitative aspects of
medical malpractices. “If malpractice is
judged inaccurately or is not clearly defined,
doctors may carry out excessive tests and
procedures to be able to cite as evidence
that they were not negligent. Likewise, if
malpractice is defined clearly but too broadly
or if awards tend to be too high, doctors may
engage in defensive medicine, inefficiently
restrict their practices, or retire.” (Limiting
tort liability for medical malpractice, 2004,
para.9).

Both these situations, from the perspective
of patients, are unwelcome, and thus the
administration needs to take care that the
patients’ rights and treatment are given the
Number One priority, no matter what
situational demands may be. For achieving
this goal, it is also necessary that there
should be a clearer and transparent
communication network between patient
and provider, which in effect, reduced the
risks of treatment dramatically. But the
communication system also needs to be
suggestive of seeking the overall well-being
of the patients and not only in terms of
securing the provider from a risky position.
It is believed that Medication errors, arising
possibly out of tort of negligence could also
be a major aspect of medical malpractices.
The only redeeming factor could be that the
errors may have arisen advertently and not
due to the gross mistake of the persons

concerned. However, it is the duty of
manufacturers of drugs to inform the
medical fraternity/ consumers about the
potential dangers of their products, etc. This
could be in the form of product literature
that accompanies the medication and
information that is passed on to the health
care practitioners during deliberations with
drug product manufacturers’
representatives.
Again, it would also be incumbent on the
part of physicians to explain drug reactions
and contraindications to patients before
administering drugs to them. Informed
consent is a crucial aspect of medical
practice and the consumers do have every
right to know about the risks and dangers
involved in using such drugs. It is also within
the ambit of consumers to refuse such drugs
that they feel could cause further health

detriment to them, and physicians need to
respect these decisions.
Another critical aspect that needs to be
enlightened is that physicians need to have
the complete background and medical
history of patients before prescribing drugs
to them. The risks of allergies could be fatal
as was seen in the case of “Harris County
Hospital District v. Estrada 872 S.W.2d 759
(Tex.1993).” (Learning objectives, 2000).
“Yet, in another important case with a
somewhat different thrust, a patient died
from an allergic reaction to a prescribed
medication. Plaintiffs for the deceased
alleged negligence. The court agreed,
concluding that the defendants failed in their
responsibility to thoroughly investigate and
review potential allergic reactions for the
deceased patient.” (Informed consent: What

every pharmacist should know: Legislative
and regulatory history, 2010, para.4).
Thus, the aspect of medical errors along with
medical malpractices could be a major
aspect in risk management, which could
indeed be suitably guarded against, through
pro-active and strategic management
decision making. Increased use of
technology like computer prescriptions
could significantly reduce medical errors to
the barest minimum and could thus reduce
the liability of physicians. Besides, more
efforts need to be made to “prevent
medication errors by maintaining adequate
stock levels of drugs on patient care units,
and ensuring that health care providers
order their patients’ drugs during regular
pharmacy hours whenever possible.”
(Granville & Rogers, 2000, p.38).

In the years to come, Medical malpractice
insurance (MMI) could be a major tool that
ensures the financial security of physicians
during the performance of their medical
functions. However prohibitive the costs of
MMI may be, it is perhaps one of the options
available to physicians against risks of
potential financial disasters in the form of
lawsuits, or medico-legal cases. It is seen that
many doctors may take recourse to unethical
processes to save their practice.
“In the health-care industry, many doctors
report ordering unnecessary tests to avoid
lawsuits” (Gryphon, 2008, para.18).
In the years to come, what is needed is to be
able to strike a right balance between the
need to keep patients’ needs uppermost
paramount and the need for the medical
profession to develop stratagems for risk
management and avoidance of potential

medical malpractices. “The issues of medical
liability, patient safety, and just
compensation for the medically injured
seem to be caught in a vicious cycle.”
(Bovbjerg & Raymond, 2003, p.22).
Many patients thus lose the right to their
legitimate claims along with the distorted
procedures and even many patients who
have the rights find themselves unable to
enforce them. There is a need for reform,
and rightly so, in seeking and establishing
norms by which the just claims of majority
claimants could be expedited, normalcy and
trust restored into the system that has long
been vitiated by governmental interference
and other bureaucratic interventions that
need to do much more in terms of seeking a
just and equitable settlement of patient
claims and insurance settlements.

“Medical malpractice law is intended to
provide physicians with an incentive to
reduce errors. Regrettably, there are two
good reasons to doubt that it currently does
a credible job. First, researchers have been
unable to detect a significant deterrent
effect. Second, physicians simply do not
believe that tort law rewards improved
quality.” (Making hospitals accountable:
Hospital-level liability could revive the
dormant deterrent power of tort liability,
2009, para.16).
Under such circumstances, it is necessary
that risk management in the health care
arena needs to be given the due importance
that is due and also undertakes ways and
means by which these aspects could be
enforced with a greater degree of
empowerment and credibility. Besides, the
aspects of patient care and comfort need to
be attended to, not only as a course of

professional ethics and being part of the
physicians’ responsibilities but also in terms
of the moral duty which physicians owe to
their patients and their caregivers.
It is the attitude of the parties that need to
undergo radical changes from the present
bellicose and confrontationist to one of
relative understanding and compatibility
within the health care provider industry. This
could, in effect, ensure a greater degree of
harmony in patient-physician relations and
could pave the way for a greater degree of
efficiency and health care effectiveness
within the industry.
Thus, Health care risk management is a
procedure that needs to be constantly
audited and monitored by the workforce
regularly. The basis of this practice is through
disallowing the occurrences of incidents.
Pro-active dedication endeared by medical

staff as well as unflinching loyalty is critical
ingredients for the success of health care
management programs. Every subsection is
liable for disallowing dangers and controlling
risks within its parameters.
Since the costs associated with occupational
medical errors and malpractice is increasing
dramatically in recent years, it has become
imperative to effectively take care of
intricate risk issues and patient safety. The
sources of additional costs could be
explained in terms of ineffective lawsuit
expenditures, insurance costs, heightened
contacts with clinical methods,
differentiation in medical care, and
insufficient support systems.
The challenges have never been greater, the
workforce is never smaller, the technology
more complicated, and patient demands
never higher. Despite all these tensions,

healthcare professionals and those who
assist them in managing the risks associated
with their responsibilities must continue to
remember that, everyday patients and their
families entrust their lives to them.
Physicians owe it to their patients to be
worthy of that trust.
Most healthcare risk managers look forward
to the opportunities ahead and are
dedicated to managing their organization’s
risk and enhancing patient safety. The future
is fraught with peril and great risk but also
great reward. Those risk managers who
accept change and think of new ways to
embed risk management principles into their
organizations to help create meaningful and
sustainable change will prosper. Those who
do not should get out of the field of medicine
right now.

Physicians, clients, politicians, and others are
very much alarmed about the rising levels of
medical wrongdoings and their indemnity
issues.
Medical malpractice and malpractice
insurance continue to be issues of great
concern to physicians, consumers,
legislators, and others. Much of the
deliberations about increasing malpractice
insurance premiums have focused upon
limiting the damage awards in malpractice
cases and some thoughts have been fostered
on the need for reforms in the insurance
sector. Another concern that has received
less public notice in malpractice discussions
of recent years is patient safety.
Safety of patients refers to the gamut of
rules, practices, and systems that govern the
need to circumvent medical injuries, and the
stratagems to obstruct medical mistakes

need to be imbued in norms of patient
welfare. Increasing medical malpractice
insurance premiums are a growing concern
in the American healthcare system. Many
physicians, professional organizations, and
lawmakers claim that the tort system
encourages frivolous lawsuits and jackpot
verdicts. To prevent a major dearth in
healthcare access, strict malpractice liability
restrictions, including caps on non-economic
damages must be mandated.
There are doubts whether a likely and total
solution for the recalcitrant malaise of
malpractices could be easily found. But if
true reforms are to be implemented in real
terms in the health care industry, it is
imperative that the reality of past failures be
understood and a more rational and
practical solution be worked out, that would
remedy the present ills, including the
prevalent tardy, costly and unjust systems

now prevailing. The ability to implement
health care reforms is a critical area,
implementation of reform packages mustn’t
be vitiated by the incompetence of
administrators to address shortcomings in
malpractice systems, which does act as a
barrier in enforcing constructive changes in
the health care industry.
Health care professionals need to find
avenues for making their vision on quality
assessment and physicians need to find a
way to make their perspective on quality
measurement and up-gradation. A change in
attitudes, skills, and associates is needed.
The success of doctors in taking care of these
assets and avoiding conflict areas with
patients would vitally affect both the future
of the profession and quality dimension and
progress in the U.S. health care system. An
alteration in how the healthcare professional
communicates with patients about harmful

medical errors has begun. Within ten years,
it is believed that the rapport between
patient and provider would be more
transparent, communicative, and robust.
Once patients are made aware of the
detrimental effects of errors in medicines
and their implementation by providers is
effectuated, it would be a step in the right
direction in renewing public confidence in
the genuineness and uprightness of the
health care system.
Risk Management symbolizes an ever-
moving procedure in a health delivery
system that can result in improved patient
care and reduced accountability. An
important mechanism of the process
includes nurturing a good relationship with
the patient, obtaining approval after
appraising all facts, practicing within
established guidelines, and careful

documentation. A triumphant risk
management program can also cause a
fruitful Continuous Quality Improvement
plan. An efficient risk management practice
does not ignore risks. Having effectual and
operational risk management shows an
insurer that your business is devoted to
decreasing and eliminating loss. It also builds
a better risk insurance mechanism for your
organization.
Risk management involves policies,
processes, and procedures that identify
potential operational and financial losses,
prevent losses whenever possible and lessen
the effects of losses that cannot be
prevented. Some of the steps that are
involved with risk management are
identifying and analyzing potential risks,
preventing and reducing the effects of
accidents, medical errors, and other injuries
and losses. Risk management must include a

heightened sensitivity to provide a safe
environment and address the emotional
needs of patients. Good relationships with
patients are very important in preventing
malpractice suits. Public relations for health
care professionals are a challenge. It is not
only a good medical practice but it is at the
very core of the problem of medical
malpractice.
Risk management is primarily designed to
protect the financial assets of an
organization by assuring adequate financial
protection against potential liability through
appropriate insurance coverage. The main
objective of risk monitoring is to reduce the
chances of identified detrimental risks. This
could be attained by enjoining risks
management into the plans.
In real terms, implementing
recommendations would envisage the

injection of several new inputs required by
physician groups to enforce the
recommendations. These could be in terms
of making provision for additional resources,
assets redistribution, realigning and
reallocating manpower and needed
workforce towards a more well defined and
charted course of action, in line with
recommendations, and above all aspects of
outside management intervention and
control in the proceedings of health centers
through outside holdings. There are
sufficient advantages in pursuing this course
of action for improved overall control and
monitoring of activities could be gained and
also raising the bar as far as improved
patient management health care
intervention techniques are concerned.
Recommendations

This study is future to be conducted using a
closed study survey of the aspects of medical
malpractices in the closed environment of
Wayne State University. For this research, it
would be necessary to conduct online
internet interviews with members of the
medical and health care providing faculty of
this institution. This would be in the form of
questions asked to them regarding their
perceptions of medical malpractices and
how to tackle such issues.
Future draft of questionnaire survey
instrument
Future draft of survey instrument:
A future random sample of 50 physicians will
be selected from the given sample
population by lots. In this survey, 25
respondents will be physicians of multiple
specialties and 25 members of the health
care team consisting of physiotherapists,

nurses, counselors, and other health care
service providers employed by WSUPG.
It is important that in a future research
survey on a sensitive topic like medical
malpractices, the prior permission of the
employers as well as aspects of ethical
consideration like privacy and confidentiality
of the information gained is also established
before the survey results are released.
Moreover, it is also necessary that the
research team declares that the data
collected would only be used for research
and not commercial usage for profits, etc.
The future research methodology will
involve first ascertaining the background of
respondents, their age, and experience, and
work duration with Wayne State University
Physician Group. The main aspects that will
need to be realized during this survey will be
in terms of identifying specific medical

outcomes or results, the role of risk
management, and specifically risk managers
in combating and alleviating areas of medical
malpractices. Besides, the gaps in physician-
patient relationships and how this could
contribute to larger incidences and
occurrences of medical malpractices are also
major areas that need to be addressed
through this survey.
Perhaps one of the major factors this survey
needs to concern itself with is the quality of
medical service provided could determine,
to a large extent, the aspects of probable
medical malpractice claims. Where there are
errors, lack of care, errors on the part of the
medical and nursing staff, without rejoinder
of risk management, the degree of
occurrences of medical malpractice cases
could indeed be high when compared to
safer, well detailed and planned quality and
degree of care provided to patients. There

are also aspects that in many cases, the
injuries sustained through medical
malpractice may go undocumented or
unclaimed, due to a lack of knowledge and
understanding among patients regarding the
modus operandi of filing of claims and their
eventual disposal by courts or relevant
authorities.
Thus, along with the knowledge of what
constitutes a case of medical malpractice
and how it comes about, it is also necessary
that patients are enlightened about the
various technical and non-technical aspects
of medical malpractice and how it impacts
the acuity of care. This research
methodology also needs to consider age,
gender, kind of illnesses for which the
aspects of medical malpractice arise, and
also the steps taken by the patients to
counter and be compensated for known
cases of medical malpractice and its

monetary value according to nature and
degree of injury sustained.
The main questions that are future to be
asked of the respondents will be as follows:
1. What are the major determinants for
assessing the causes and impacts of
medical malpractices?
2. How does the aspect of
communication, or lack of it, affect the
health of patients?
3. Are the risks of litigating damages in
the areas of medical malpractices real?
4. What are the main purposes of
Medical malpractices insurance?
5. What role does objectivity and
pragmatism play in government medical
malpractices?
6. How can blame be attributable and
accountable in malpractice cases?

7. How the aspects of errors and
mistakes could be detected and avoided?
Analysis
Further, the findings of the research
proposal may prove that the majority of the
issues arising are due to a lack of
communication between the people
involved- the patients, care providers, and
the public in general. Moreover, it is seen
that patients place trust and reliance on the
advice and course of medication offered by
professional health care specialists, and
therefore, if malpractices or lack of care is
established, it could well be ending in
lawsuits in which the party at fault would
have to pay up a large sum as compensation
for damages and also other compensation as
decided by the Courts. Besides, several other
aspects, like the degree of care that was
necessary to exercise, that which was given

and the gaps in treatment are all major
aspects that impact the patient’s perception
and attitude towards caregivers.
The future respondents may mention that
the legal protection may be sought to be
made available to patients, especially those
needing long-term intensive care as a major
aspect. Often, health care professionals are
overburdened with cases, and the lack of a
suitable patient care ratio may also tend
caregiving to be marginalized, specialized
and individual care may, more often than
not, be the privilege of the affluent class.
The results of the survey seem to indicate
that more degree of care needs to be taken
by providers in the health care industry to
avoid patient litigation and cases of medical
malpractice. “The purpose of medical
malpractice insurance is twofold:

1. to protect health care practitioners
from the negative economic
consequences of being found negligent
in their medical practices; and
2. to provide compensation for
individuals who suffer harm from
negligent doctors” (Medical malpractice
insurance rates, 2003, Purpose of
medical malpractice insurance, para.2).
Coming to the legal aspects that govern
medical malpractices and their invocation, it
could be said that while laws may exist, they
need to be applied contextually to achieve
results. It could also be seen that more
emphasis needs to be placed on the
objectivity part of treatment and not it’s the
subjective part. Further, it is also seen that
more relevance and importance needs to be
given to the right modes of treatment and
follow the standard and specified methods,

rather than depend upon methods that are
open to controversy or are not well
opinionated.
The next aspect that needs to be considered
in the context of medical malpractice could
be in terms of how blame could be
attributable and accountable and how they
are presented in a court setting. It is seen
that proper maintenance of official records
of patients and their profiles needs to be
made available on request too
risk managers and insurance companies. The
records and database speak volumes about
the degree of care and medication that has
been followed, and through maintenance of
proper records and archives, risk managers
would be in a much better position to
ascertain losses and pin accountability. This
could also be in terms of the fact that greater
impact and risk management practices need

to be imbued to gain better resource
allocation to patients.
Coming to the aspects of how errors and
risks could be pinpointed, it could be said
that the documents available to insurance
companies, risk managers, and appropriate
management concerns could, to a large
extent, determine the amount and scope of
losses and how the compensatory amounts
could be gained. Further, it is also possible
that a more focused and deeper insight to be
established that could address the finer
issues that underpin medical malpractices in
the context of the health care industry.
From the future deliberations with health
risk managers and their views on the aspects
of risk management, it is abundantly clear
that there needs to be a sound and plausible
health care management system that could
address all facets of patient-provider caring

and also create a congenial and positive
health care environment that could enhance
patient treatment and early recovery.
Moreover, it is seen that in the current
settings, it is important that a cohesive and
well-structured risk management plan,
addressing all major areas of public health
accountability and patient care, irrespective
of the specifics of the case and local
influences, need to be formulated and
executed to save future litigation and
redundant health care costs. Thus, “all
health care providers must focus on
enhancing the effectiveness of their risk
management programs” (Effective health
care risk management programs, n.d., p.8).
Those who are unable to do so would be
marginalized for failing to provide suitable
patient safety protections and would surely
find insurance coverage for professional

liabilities and injuries difficult to obtain and
enforce.
Thus, it is not only in the best interest of the
patients but also that of the provider
institution to enforce a disciplined and well-
rounded risk management policy that could
attend to all areas of patient care and its
implications on the accidental aspects of
health care business. Providers who neglect
or undermine such schemes may be
seriously disadvantaged over time and may
find themselves in a deeper quagmire than
before.
For the Risk Management Program to remain
successful, the researcher also recommends
the enforcement of a robust action plan that
envisages, among others, the setting up of a
National Center for Patient Safety. This
would ensure the development of an error-
free reporting system that guarantees

confidentiality and privacy of patients’
records. It also helps in raising the bar about
performance standards and safety
commitments within health care
professional groups and accreditation
boards.
Keeping in view the key factor of ensuring
the best health and welfare interests, health
care centers must implement a high degree
of safety standards at the level of patient
care delivery systems. There is the need for
constant internal audit and monitoring to
ensure that these factors are being
consistently delivered and sustained through
prudent and judicious planning and
organizing of patient welfare programs,
before, during, and after the provision of
health care services in an institutionalized
setting.

How do our recommendations match with
things being carried out in the Wayne State
University Group?
The need for a constructive and patient-
centric approach has been at the heart of our
recommendations, combined with a sound
and plausible health care safety
management system that could address all
facets relating to the provision of optimum
patient-provider care systems.
Hospital administration has adopted many
schemes to update quality and patient
security during the duration of stay in
hospital settings.
This has also been the guiding principle of
the Wayne State University Physician Group.
Moreover, aspects like planning and
organizing individualistic patient care, and
safe caring which has been mentioned in this

study, are regularly practiced at this health
care setting at WSUG.
One of the major recommendations that
could be given is that the patient’s best
interests supplant other factors, especially in
the case of elderly, or very young patients,
who may not possess the wherewithals to
take care of their health and well-being,
Health is an aspect whose importance is only
known after a
life-threatening crisis develops. Thus, it
becomes necessary to inculcate pro-active
and pre-emptive measures to circumvent, or
even prevent such occurrences as humanly
possible. The preventive aspect of health
care is even more significant than ultimately
curing diseases, especially when many kinds
of ailments do not carry ID cards when it is
ushered into the lives of patients and their
apparent well-being. Diseases are quite

capable of causing more detriment than
could be visualized and given
encouragement and support through
medical malpractice and high uncovered
risks could provide more than what patients
and their care providers could have
bargained for.
Instrumentation
Questionnaire Survey (considered in analysis
section)
The main survey questions to be asked of the
respondents will be as follows:
1. What are the major determinants for
assessing the causes and impacts of
medical malpractices?
2. How does the aspect of
communication, or lack of it, affect the
health of patients?

3. Are the risks of litigating damages in
the areas of medical malpractices real?
4. What are the main purposes of
Medical malpractices insurance?
5. What role does objectivity and
pragmatism play in government medical
malpractices?
6. How can blame be attributable and
accountable in malpractice cases?
7. How the aspects of errors and
mistakes could be detected and avoided?
Reference List
Acute care, disability, and rehabilitation:
Public health burden: Priorities. (2006). CDC
Injury Center. Web.
Acute care, disability, and rehabilitation:
Public health burden. (2006). CDC Injury
Center. Web.

Annotated resources: Sentinel events.
(2009). The Joint Commission. Web.
Bovbjerg, R.R., & Raymond, B.
(2003). Patient safety, just compensation,
and medical liability reform. Kaiser
Permanente. Web.
Effective health care risk management
programs: Components for success:
Conclusion. (n.d.). Chubb Health Care. 8.
Granville, R.L., & Rogers, W.J.
(2000). Payment of federal malpractice
claims. Legal Medicine. Web.
Grose, V L. (2005). Managing medical
malpractice risk via system science:
Abstract. Journal of Medical systems, 6 (1),
89-103. Springer Netherlands. Web.
Gryphon, M. (2008). Greater justice, lower
cost: How a “loser pays” rule would improve
the American legal system. Civil Justice

Report. Manhattan Institute for Policy
Research. Web.
Informed consent: What every pharmacist
should know: Legislative and regulatory
history. (2010). Medscape Today. Web.
Learning objectives. (2000). Web.
Limiting tort liability for medical malpractice.
(2004). CBO. Web.
Making hospitals accountable: Hospital-level
liability could revive the dormant deterrent
power of tort liability. (2009). Cato Institute.
Web.
Medical malpractice insurance rates:
Chapter 1: Purpose of medical malpractice
insurance. (2003). Connecticut General
Assembly: Legislative Program Review and
Investigations Committee. Web.
Medical malpractice jury trial verdicts. (n.d.).

Sentinel event statistics as of June 30, 2009.
(n.d.). The Joint Commission. Web.
Medical professional liability insurance
trends in Asia: Malaysia. (n.d.). Web.
News: New online brochure hopes to get
patients more involved in protecting
themselves. (2005). Drug Danger: Providing
Consumer Information on Dangerous Drugs
and Medication Errors. Web.
Peterson, S. (2005). Developing risk-
management protocols in assisted living:
Assisted living has its litigation traps for the
unwary. All Business, A D & B Company:
Simple Solutions. Powerful Advice. Web.
Pratt, J. (2009). Long-term care: Managing
across the continuum (3rd ed.). Jones &
Bartlett Publishers.
Preventing medication errors: Quality chasm
series. (2009). Institute of Medicine of the
National Academies. Web.

Prognosis E-News: Fieger, howard debate
merit of health courts. (2005). School of
Medicine. Wayne State University. Web.
Reid, D J., & Reid, W H. (2009). Research
article: Terrorism-related risk management
for healthcare facilities. Behavioral Sciences
& the Law, 23 (4), 591-601. John Wiley &
Sons, Ltd. Web.
Risk management: The steps of risk
management. (2002). Arch National
Resource center: Fact Sheet Number 17.
Web.
Shandell, R E., & Smith, P. (1990). The
preparation and trial of medical malpractice
cases. Law Journal Press.
Umbdenstock, R. (2009). In this area of
reform, it’s already full steam ahead.
American Hospital Association. Web.
Wayne state university and Detroit medical
center settle a dispute over compensation for

physician services. (2009). Wayne State
University. Web.
Wells Fargo Healthcare: Operational risk
management & safety assessment. (n.d.).
2009 WFIS Operational Risk Management &
Safety Assessment.
White, B S., & Traux, D. (2007). The nurse
practitioner in long-term care: Guidelines for
clinical practice. Jones & Bartlett Publishers.
Xu, X., Siefert, K A., Jacobson, P D., Lory, J R.,
Ransom, S B., & Arbor, A. (2008). The effects
of medical liability on obstetric care supply in
Michigan: Materials and methods:
Survey. Am J Obstet Gynecol, 198 (2),
205.e1-205.e9. Pub Med Central. Web.
Appendix 1
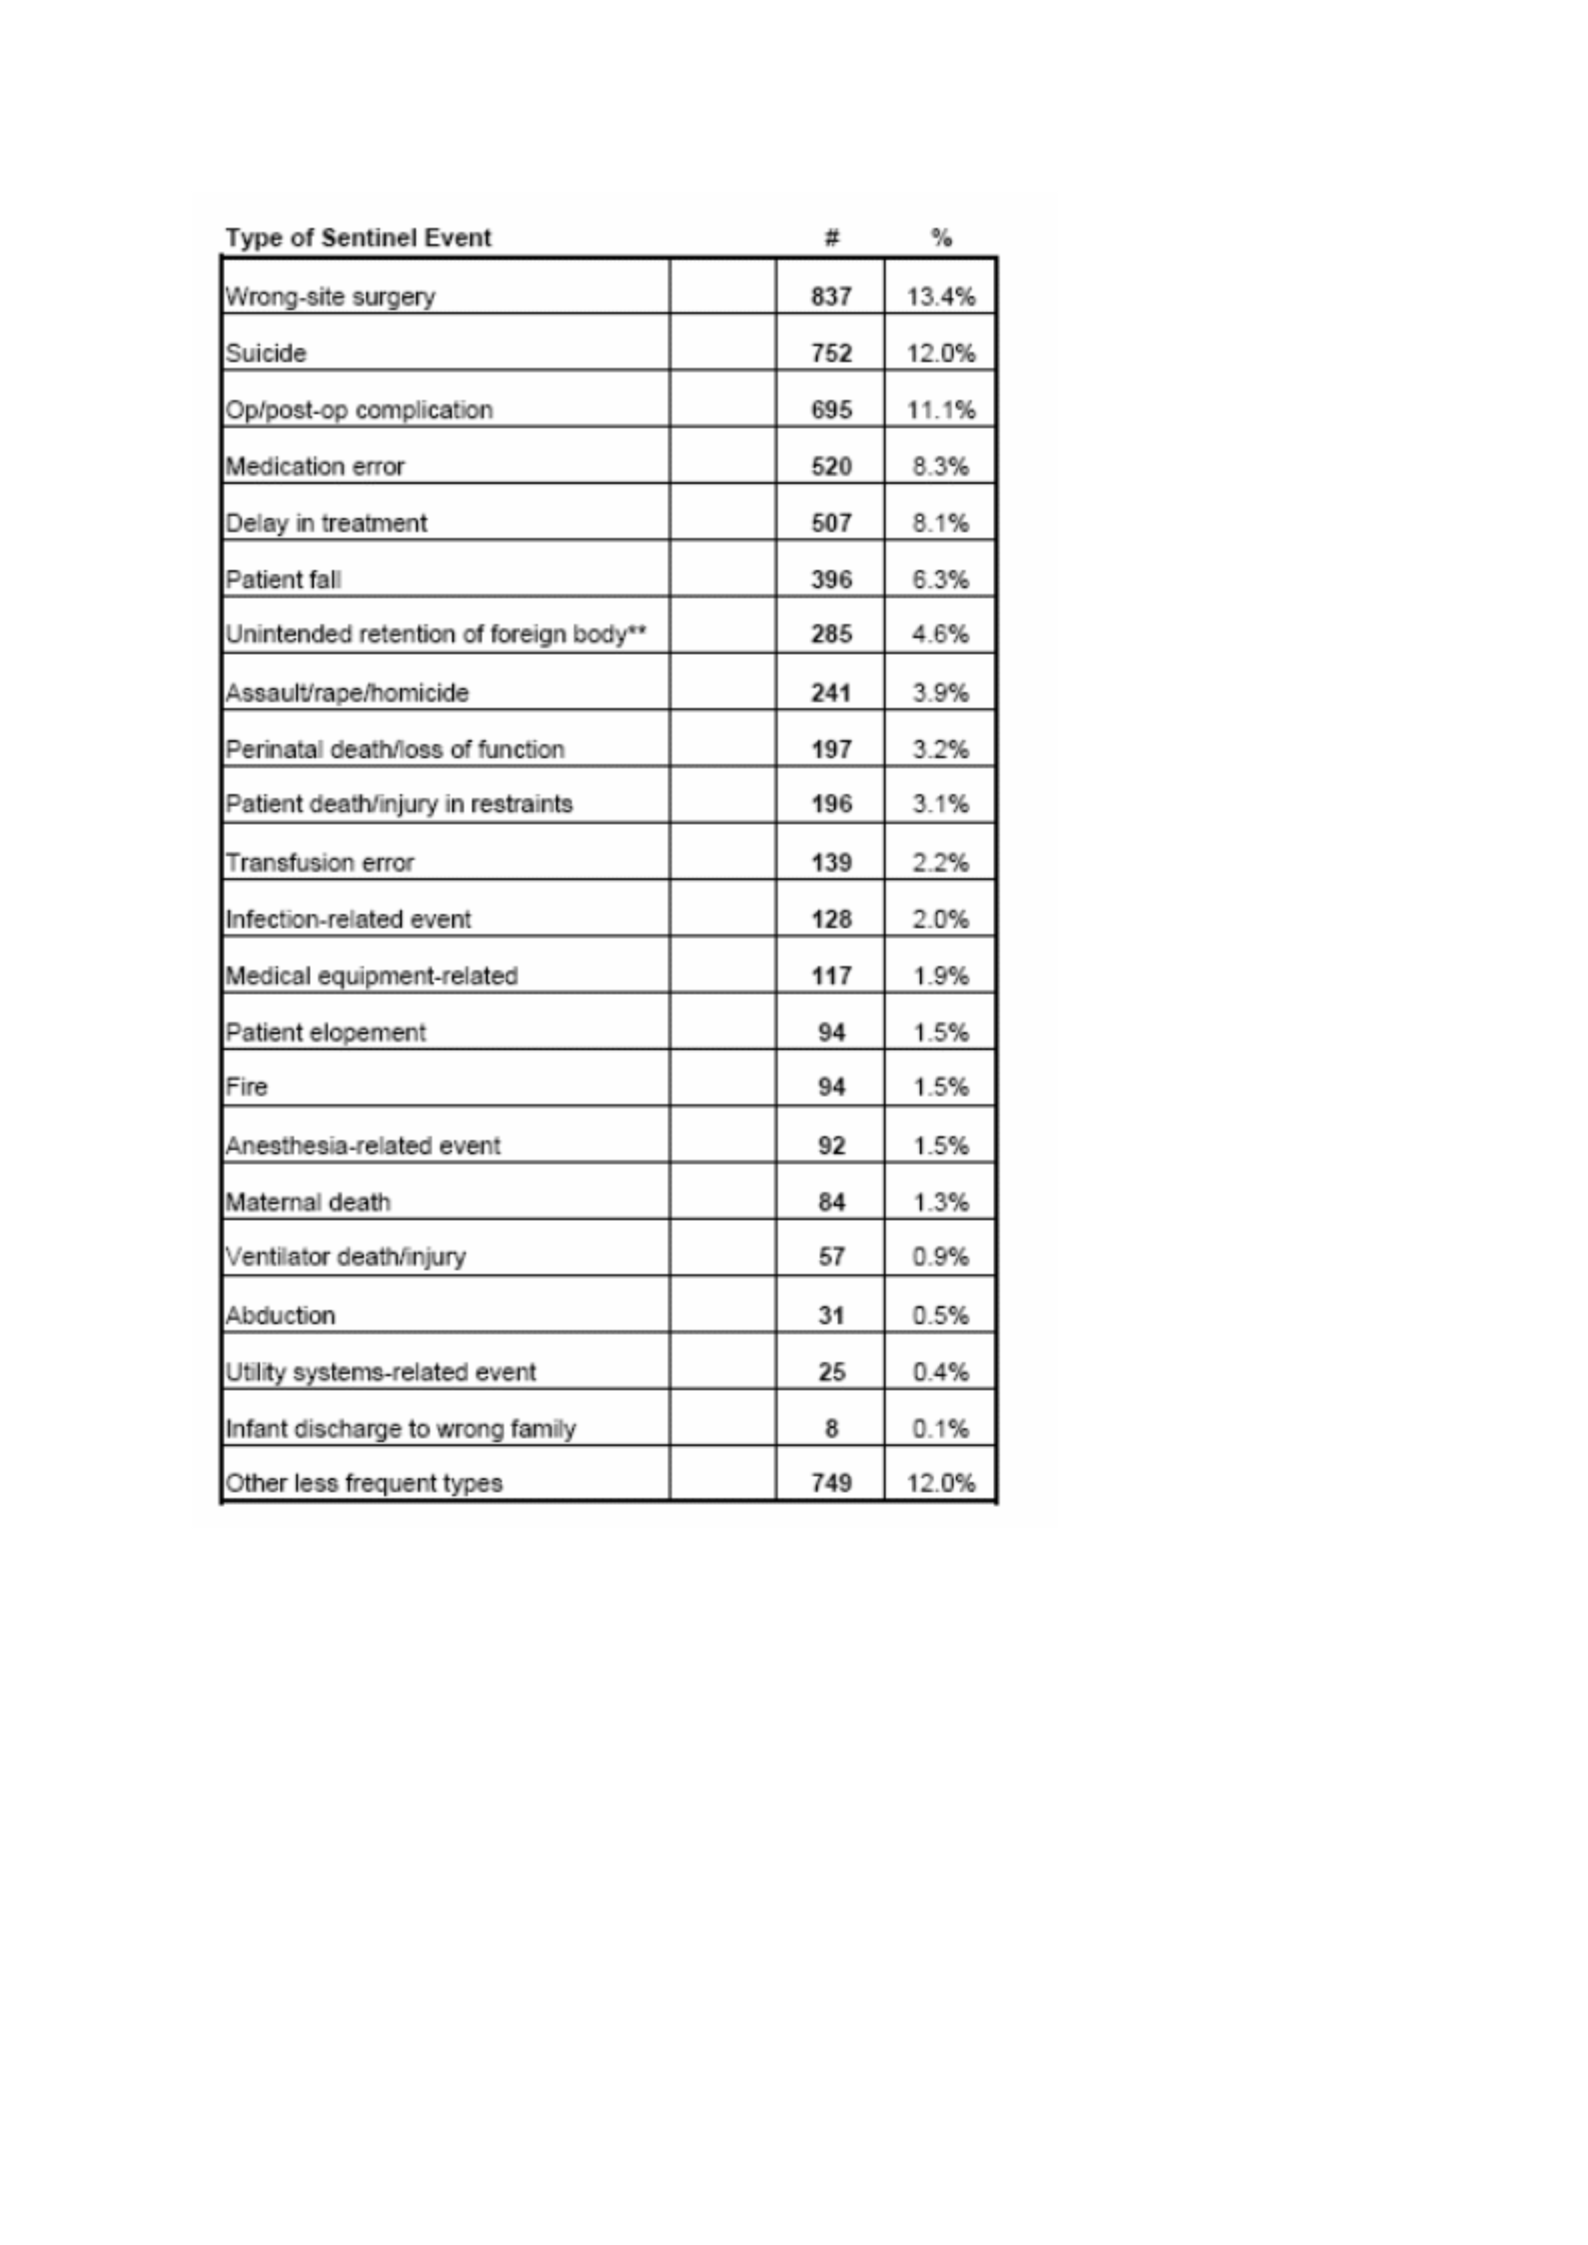
Joint Commission National Statistics of
Sentinel Events.
Appendix 2
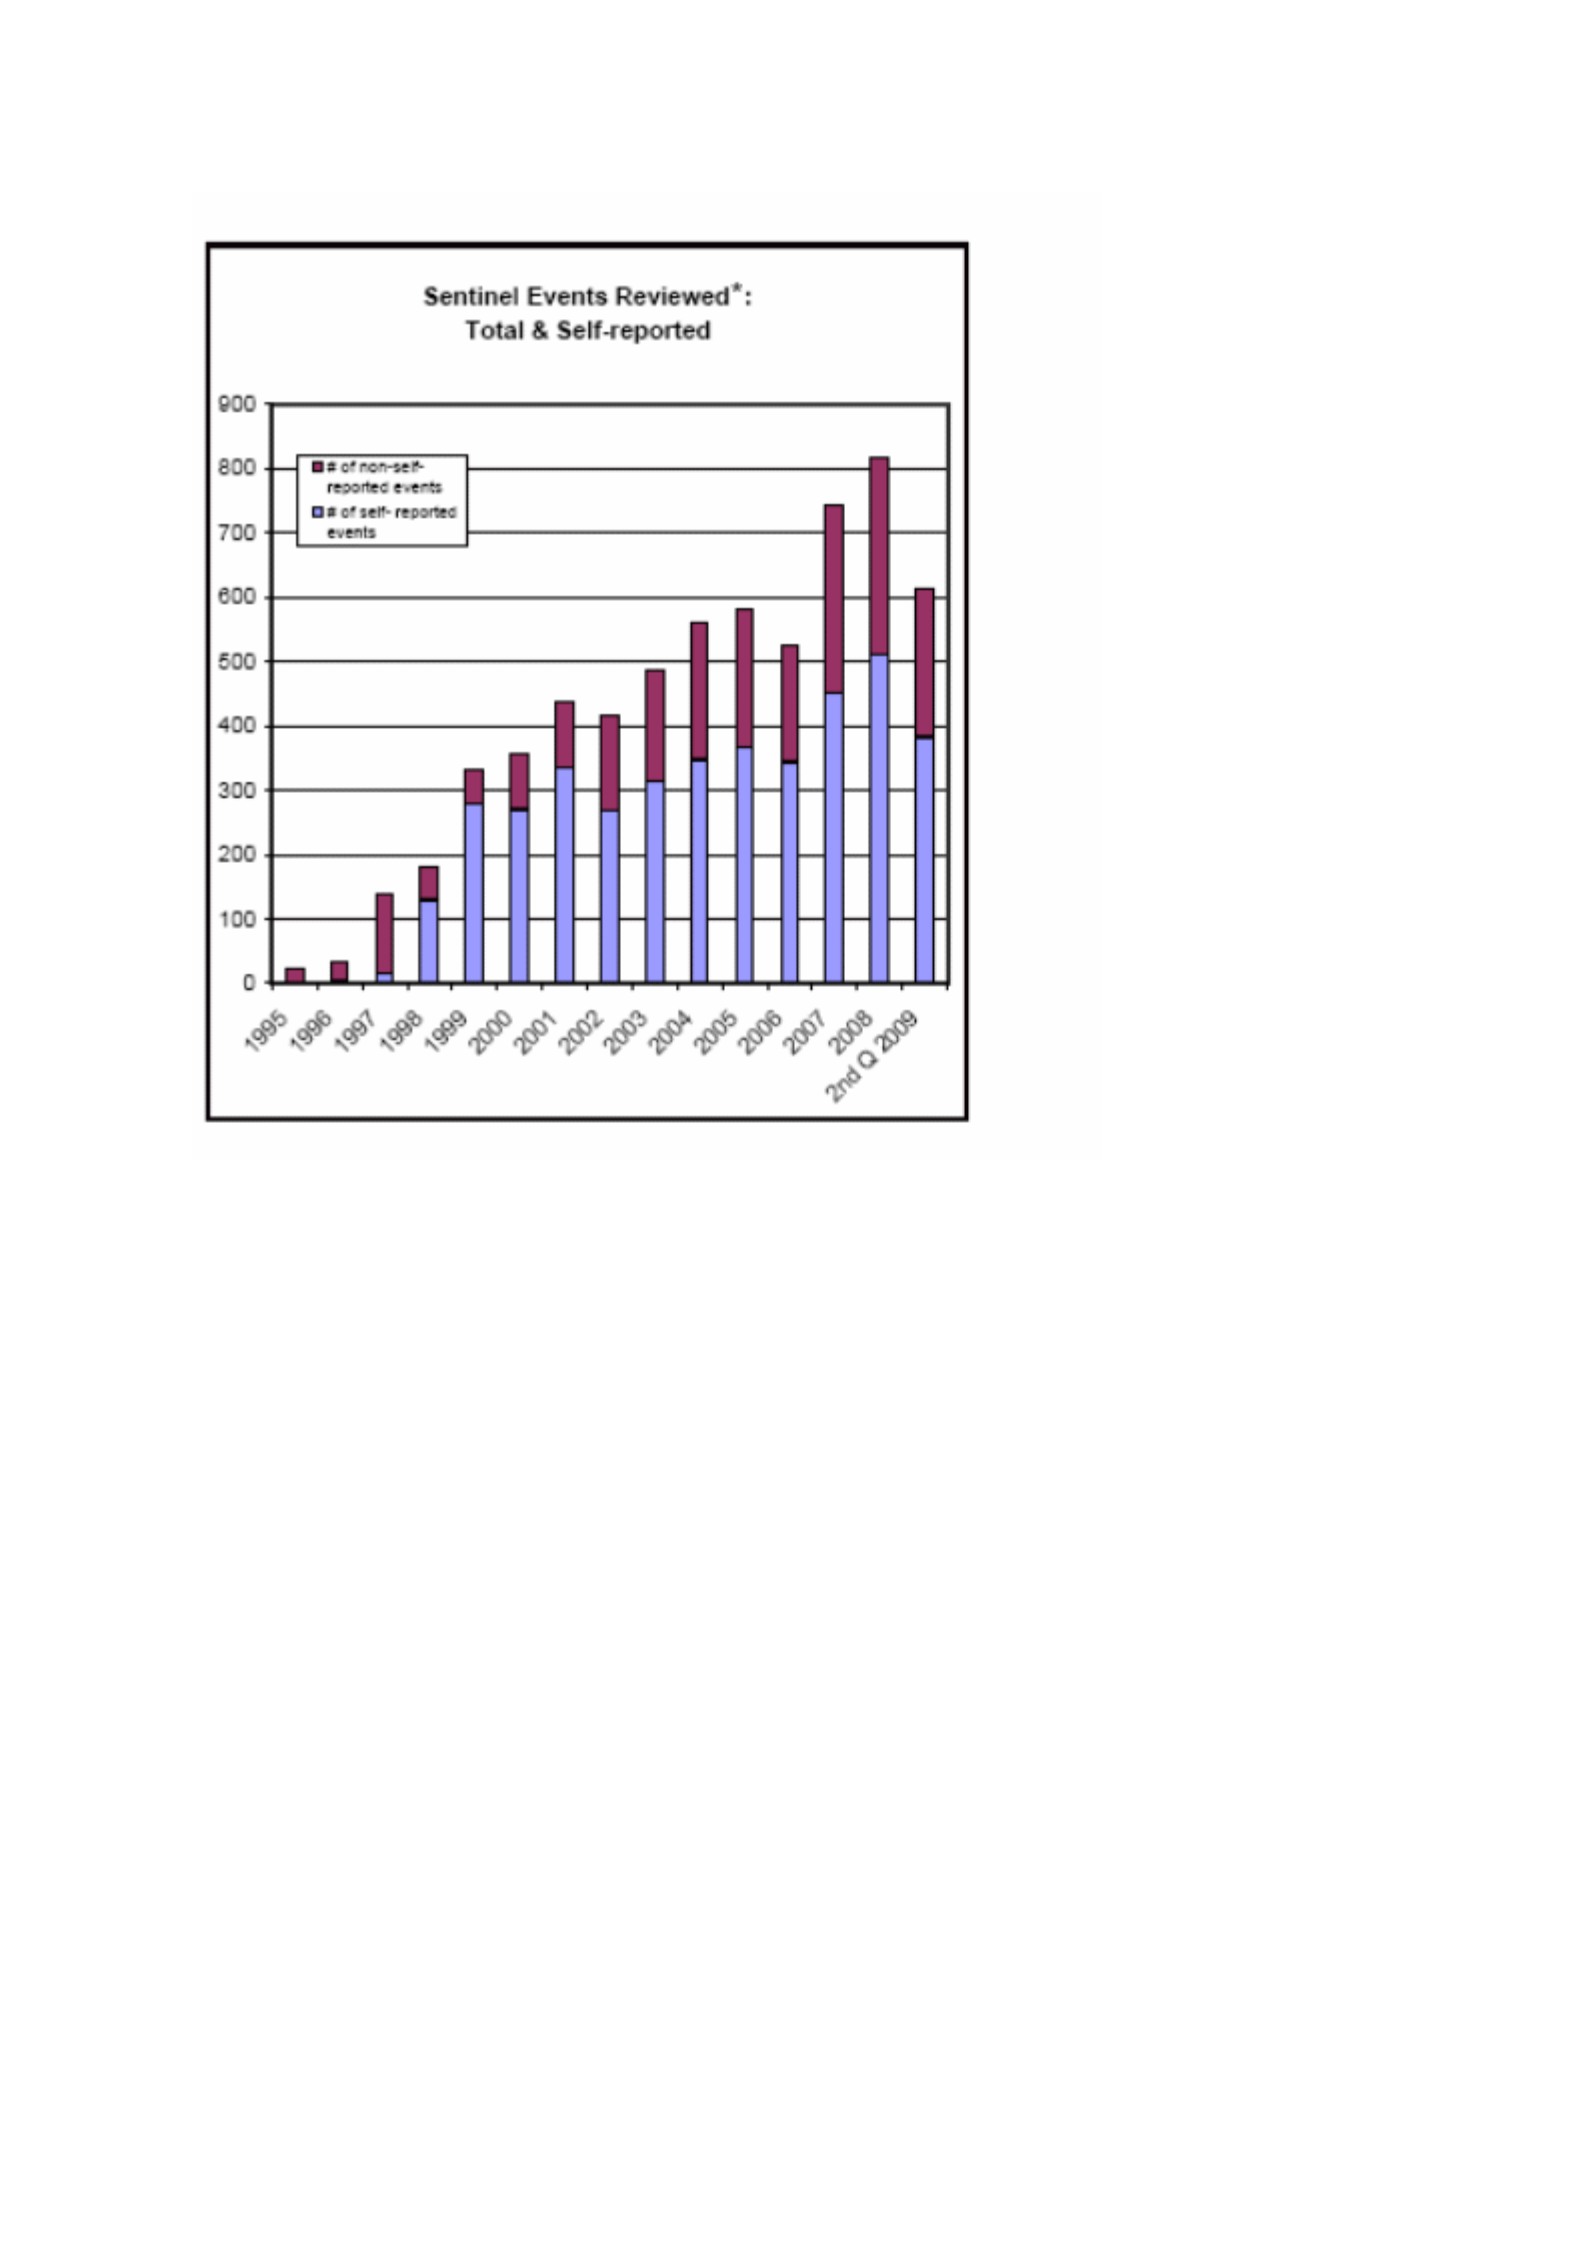
Joint Commission National Statistics of
Sentinel Events.

