


1
Sexual Education, Sexual Initiation, and Contraceptive
Use Among African American Young Women
Chapter 1: Introduction to the Study
Introduction
A nation's health is often judged by its women and children's health, with
unintended pregnancy serving as a key indicator of a population’s reproductive health
(Finer & Zolna, 2014). Unintended pregnancy, whether unwanted or mistimed, is
associated with emotional, social, and economic outcomes which in turn may lead to
further disparities in morbidity and mortality (Carter, Kraft, Hock-Long, &
HatfieldTimajchy, 2013; James & Rashid, 2013; U.S. Department of Health & Human
Services. 2019). Health outcomes among mothers who experience unintended pregnancy
include delayed prenatal care, reduced breastfeeding, depression, delivery of infants with
low birth weight and congenital disabilities, and reduced average income compared to
other women (James & Rashid, 2013; USDHHS, 2019). Infants born due to unintended
pregnancies are at increased risk of poor mental, physical, and behavioral health in
adolescence and lower educational attainment (James & Rashid, 2013; USDHHS, 2019).
These health outcomes associated with unintended pregnancy suggest that reducing its
occurrence may substantially impact public health practices.
Within the United States, two groups among those at the highest risk of
unintended pregnancy are women aged 18–24 and those of African American descent
(USDHHS, 2019). African American women aged 18–24 are at higher risk for

unintended pregnancy and sexually transmitted infections (STIs) due to non-use,
inconsistent, or improper use of contraception, as well as failure to use dual contraceptive
methods (Craig, Dehlendorf, Borrero, Harper, & Rocca, 2014). These are topics covered
during formal sexual health education (FSHE). The purpose of this quantitative study was
to investigate the extent to which knowledge gained through FSHE impacts sexual
initiation and contraceptive use and selection among African American women aged 18–
24 in the United States who have sex with men.
An understanding of the impact of FSHE may help sexual health educators and
practitioners provide African American young women with the required knowledge and
skills to delay sexual initiation and consistently and properly use preference and intention
matched contraceptive methods. African American young women may apply knowledge
and skills to prevent unintended pregnancy, and by extension, may decrease adverse
maternal and child-associated public health outcomes. Doing so may lead to social
change by positively impacting African American young women's socioeconomic status,
and by extension, their children, which may improve associated social, educational, and
public health outcomes for both populations.
Covered in this is chapter is background information about gaps in public health
knowledge regarding African American young women’s sexual initiation and
contraceptive knowledge, selection, use, and unintended pregnancy. The problem
statement, research design, and methodology, which drove this research, will also be

3
discussed. Key terms are defined, and assumptions, limitations, and significance of the
study are identified and explored. This chapter is followed by the literature review in
Chapter 2 and the discussion of methodology in Chapter 3.
Background
FSHE promotes safer sexual behaviors for young adults, including delayed sexual
initiation and increased and correct contraceptive usage beginning with the first sexual
encounter (Lindberg & Maddow-Zimet, 2012). While teen and adolescent pregnancy and
FSHE in the United States has been the subject of national campaigns, unintended
pregnancy and FSHE in young adult women have received minimal attention. This lack
of attention may be due to the classification of this age group as adults and the false
assumption that they are equipped with knowledge regarding sexual and reproductive
health.
According to the Centers for Disease Control and Prevention (2019), out of the
88% of required U.S. high school students who received FSHE as a course, 76.3%
received education that abstinence as the best way to prevent human immunodeficiency
virus (HIV) and other STIs. In this same cohort, 35% learned how to use a condom
correctly, 52.7% received guidance on how to obtain condoms, and 54.9% learned about
the importance of dual contraceptive methods in preventing pregnancy and STIs (CDC,
2019). Among high schools that offered pregnancy prevention courses, the mean number
of required instruction hours was 4.2(CDC, 2019). Among high school course instructors,
12.6% received professional development on pregnancy prevention during the two years

before the study, while 14.2% wanted to receive professional development on topics
taught in their courses (CDC, 2019d).
This lack of comprehensive sexual health education (CSHE) translates into risky
sexual health behaviors. Nationally, 39% of U.S. high school students had sexual
intercourse, with the number being higher among African American students at 45.8%
(CDC, 2019). Among this cohort, 3.4% experienced sexual initiation before the age of 13
compared to 7.5% of African American students (CDC, 2019). Among this cohort, 46.2%
of sexually active high school students did not use a condom during their last sexual
encounter compared to 47.9% of African American students; 79.3% did not use birth
control pills compared to 86.8% of African American students; 95.9% did not use an
intrauterine device (IUD) or hormonal implant compared to 96.7% of African American
students; 95.3% did not use a hormonal shot, patch, or birth control ring to prevent
pregnancy or STIs compared to 94% of African American students; and 91.2% did not
use dual contraceptive methods compared to 77.5% of African American students (CDC,
2019).
More than 400 risk and protective factors are associated with pregnancy, sexual
behaviors, and contraception use in adolescents; however, their associations among
young adults are undetermined ((Kornides, Kistantas, Lindley, & Wu, 2015). It is
assumed that these factors and lack of contraceptive knowledge seen among high school
students carry over to young adulthood, where individuals explore their sexual freedom
and place themselves at risk for unintended pregnancy. Among college students who

5
received FSHE, 44.7% received pregnancy prevention information from their university
or college, and 49.5% did not use a contraceptive method the last time they had
intercourse (American College Health Association, 2017). Within this same cohort,
47.2% did not use birth control pills, 71.2% did not use an IUD, hormonal implant, shot,
patch, or birth control ring to prevent pregnancy, and 47.2% did not use dual
contraceptive methods (ACHA, 2017). College students predominantly used birth control
pills (58.2%), male condoms (63.1%), and withdrawal (35.1%) for pregnancy prevention
(ACHA, 2017). Based on data from these two surveys, contraceptive use is similar among
high school and college students surveyed, demonstrating opportunities and a need for
improved initial and supplemental sexual health education among college students.
Young adult pregnancies account for 55% of unintended pregnancies each year,
with one in six non-Hispanic Black women aged 20–24 experiencing an unintended
pregnancy (USDHHS, 2019). Trussell and Wynn (2008) suggested that the three best
strategies for reducing unintended pregnancy are to increase consistent and proper
contraceptive use, methods that do not require strict adherence, and dual contraceptive
methods. African American women aged 18–24 are at higher risk for unintended
pregnancy due to non-use of contraception, inconsistent or improper use of contraception,
and failure to use dual contraceptive methods (Craig et al., 2014). Efforts to reduce
unintended pregnancy should focus on increasing and improving FSHE regarding correct
usage and access to modern contraceptive services and methods, especially long-acting
reversible contraceptives (LARC), which do not require strict adherence (Tibaijuka et al.,

2017). Despite LARC methods being more cost effective, efficient, and not requiring
stricter adherence compared to more common short-acting contraceptives, fewer than 5%
of young adult women (Rubin, Felsher, Korich, & Jacobs, 2016; Tibaijuka et al., 2017).
LARC usage is lower among African American young women, which may be due to
medical mistrust resulting from historical reproductive and medical abuse (Jackson,
Karasek, Dehlendorf, & Foster, 2016).
Problem Statement
Despite recent contributions in contraceptive research, information involving
selection among African American young women has not been fully characterized.
Research examining contraceptive use among African American women has been limited
to either small qualitative studies or large surveys focusing on nonuse. Contraceptive
selection may be inhibited or facilitated by pregnancy intentions, physical and financial
access to methods, personal and vicarious experiences, and partner and social network
preferences. Underuse may be due to misinformation and misperceptions regarding
contraceptive efficacy, side effects, impact on future fertility, lack of social support
regarding contraceptive use, pregnancy ambivalence, and underestimations of pregnancy
risks (Craig et al., 2014). It also may be further exacerbated by historical reproductive
abuse and medical mistrust in communities of color. African American young women
report earlier sexual initiation and are more likely to experience an unwanted or mistimed
pregnancy than their peers (Moilanen, Leary, Watson, & Ottley, 2018). Women who
experience early sexual initiation are less likely to use contraception and are prone to an

7
increased risk for depression and lower self-esteem (Golden, Furman, & Collibee, 2016;
Lanier, Stewart, Schensul, & Guthrie, 2018). CSHE may have a protective influence on
early sexual initiation (Bourke, Boduszek, Kelleher, McBride, & Morgan, 2014).
Increasing access to CSHE, which highlights modern contraceptive methods, may
mitigate these factors.
The purpose of this study was to investigate the extent to which knowledge gained
through FSHE impacts sexual initiation and contraceptive use and selection among
African American women between 18 and 24 years old in the United States who have sex
with men. FSHE varies by state in terms of medical accuracy and comprehensiveness
regarding abstinence and contraceptive methods. Vicarious and historical experience may
also impact contraceptive use, contraceptive selection, and sexual initiation. Increasing
public health providers’ knowledge regarding the impact of FSHE on sexual initiation
and contraceptive use and selection among African American women between 18 and 24
years old in the United States may lead to the development of interventions designed to
prevent unintended pregnancies through increased consistent preference and intention
matched contraceptive use and improve maternal health and reduce adverse birth
outcomes, continued public health target areas among African
American young women.
Purpose of the Study
The nature of this quantitative cross-sectional analysis of the 2015–2017 National
Survey of Family Growth (NSFG) was to explore receipt of FSHE and the impact it had

on sexual initiation and contraceptive use and selection among African American women
aged 18–24 in the United States who have sex with men. This information may highlight
the importance and increase the provision of FSHE, which may raise the age of sexual
initiation, increase consistent use of preference and intention matched contraceptives, and
reduce contraceptive failures due to improper use.
Research Questions and Hypotheses
The research questions (RQ) for this study are as follows:
RQ1: Is there an association between the type of FSHE received and the age of
sexual initiation among sexually active African American women aged 18–24 who have
sex with men?
H01: There is no association between the type of FSHE received and the age of
sexual initiation among sexually active African American women aged 18–24 who have
sex with men.
H11: There is an association between the type of FSHE received and the age of
sexual initiation among sexually active African American women aged 18–24 who have
sex with men.
RQ2: Is there an association between the type of FSHE received and contraceptive
use at sexual initiation for sexually active African American women aged
18–24 who have sex with men?

9
H02: There is no association between the type of FSHE received and contraceptive
use at sexual initiation among sexually active African American women aged 18–24 who
have sex with men.
H12: There is an association between the type of FSHE received and contraceptive
use at sexual initiation among African American women aged 18–24 who have sex with
men.
RQ3: Is there an association between the type of FSHE received and the
effectiveness of contraceptive methods selected at sexual initiation by sexually active
African American women aged 18–24 who have sex with men?
H03: There is no association between the type of FSHE received and the
effectiveness of contraceptive methods selected at sexual initiation by sexually active
African American women aged 18–24 who have sex with men.
H13: There is an association between the type of FSHE received and the effectiveness
of the contraceptive method selected at sexual initiation by sexually active
African American women aged 18–24 who have sex with men.
RQ4: Is there an association between the type of FSHE received and the
effectiveness of contraceptive methods primarily selected by sexually active African
American women aged 18–24 who have sex with men at last intercourse within the past
12 months?

H04: There is no association between the type of FSHE received and the
effectiveness of the contraceptive method primarily selected by sexually active African
American women aged 18–24 who have sex with men at last intercourse within the past
12 months.
H14: There is an association between the type of FSHE received and the
effectiveness of contraceptive methods primarily selected by sexually active African
American women aged 18–24 who have sex with men at last intercourse within the past
12 months.
Theoretical Foundation
The reasoned-action approach (RAA) drove this investigation regarding the extent
to which knowledge gained through FSHE impacts contraceptive selection, contraceptive
use, and sexual initiation among African American women aged 18–24 in the United
States who have sex with men. The RAA identifies personal, social, and control-related
factors that impact behavior (Hagger, Polet, & Lintunen, 2018). In this study, the RAA
lent insight into the attitudes, norms, and self-efficacy associated with contraception
intention and decision-making.
Attitudes toward contraceptive behavior include beliefs about benefits or
consequences of performing the behavior, often influenced by knowledge (Fishbein,
2008). Racial/ethnic disparities involving contraceptive knowledge exist, and there is an
association shown between lack of contraceptive knowledge and low contraceptive use.
Not having CSHE is associated with use of less effective contraceptive methods (LECM)
and increased unintended pregnancy (Kim, Dagher, & Chen, 2016).

11
Perceived social norms toward sexuality, contraceptive use, and pregnancy are
formed based on vicarious experiences. African American women are exposed to higher
teen and single parenthood rates, earlier sexual initiation, and use contraception less
effectively (Barber, Yarger, & Gatny, 2015). African American women who perceive
negative peer norms involving contraceptive use are more likely to be inconsistent in
contraceptive usage and use LECMs (Crosby et al., 2013). Carter et al. (2012) suggested
that anecdotal information and personal experiences may supersede formal education in
influencing African American young women’s contraception decision making.
Self-efficacy involving contraceptive behaviors includes availability of resources,
affordability, access, and skills needed to perform health behavior (Fishbein, 2008;
Nisson & Earl, 2016). Uninsured and underinsured women are more likely not to use
contraception or use LECM and be at increased risk for unintended pregnancy compared
to those with private insurance (Kim et al., 2016). CSHE increases self-efficacy and the
skill needed to select and use more effective contraception.
Conceptual Framework
The purpose of this study was to use the RAA to investigate the extent to which
knowledge gained through FSHE impacts sexual initiation and contraceptive use and
selection among African American women aged 18–24 in the United States who have sex
with men. The first step when using the RAA is to describe and define the behaviors of
interest (Fishbein, 2008). Sexual initiation and contraceptive use and selection, as
selfreported by African American young women who have sex with men, is the behavior
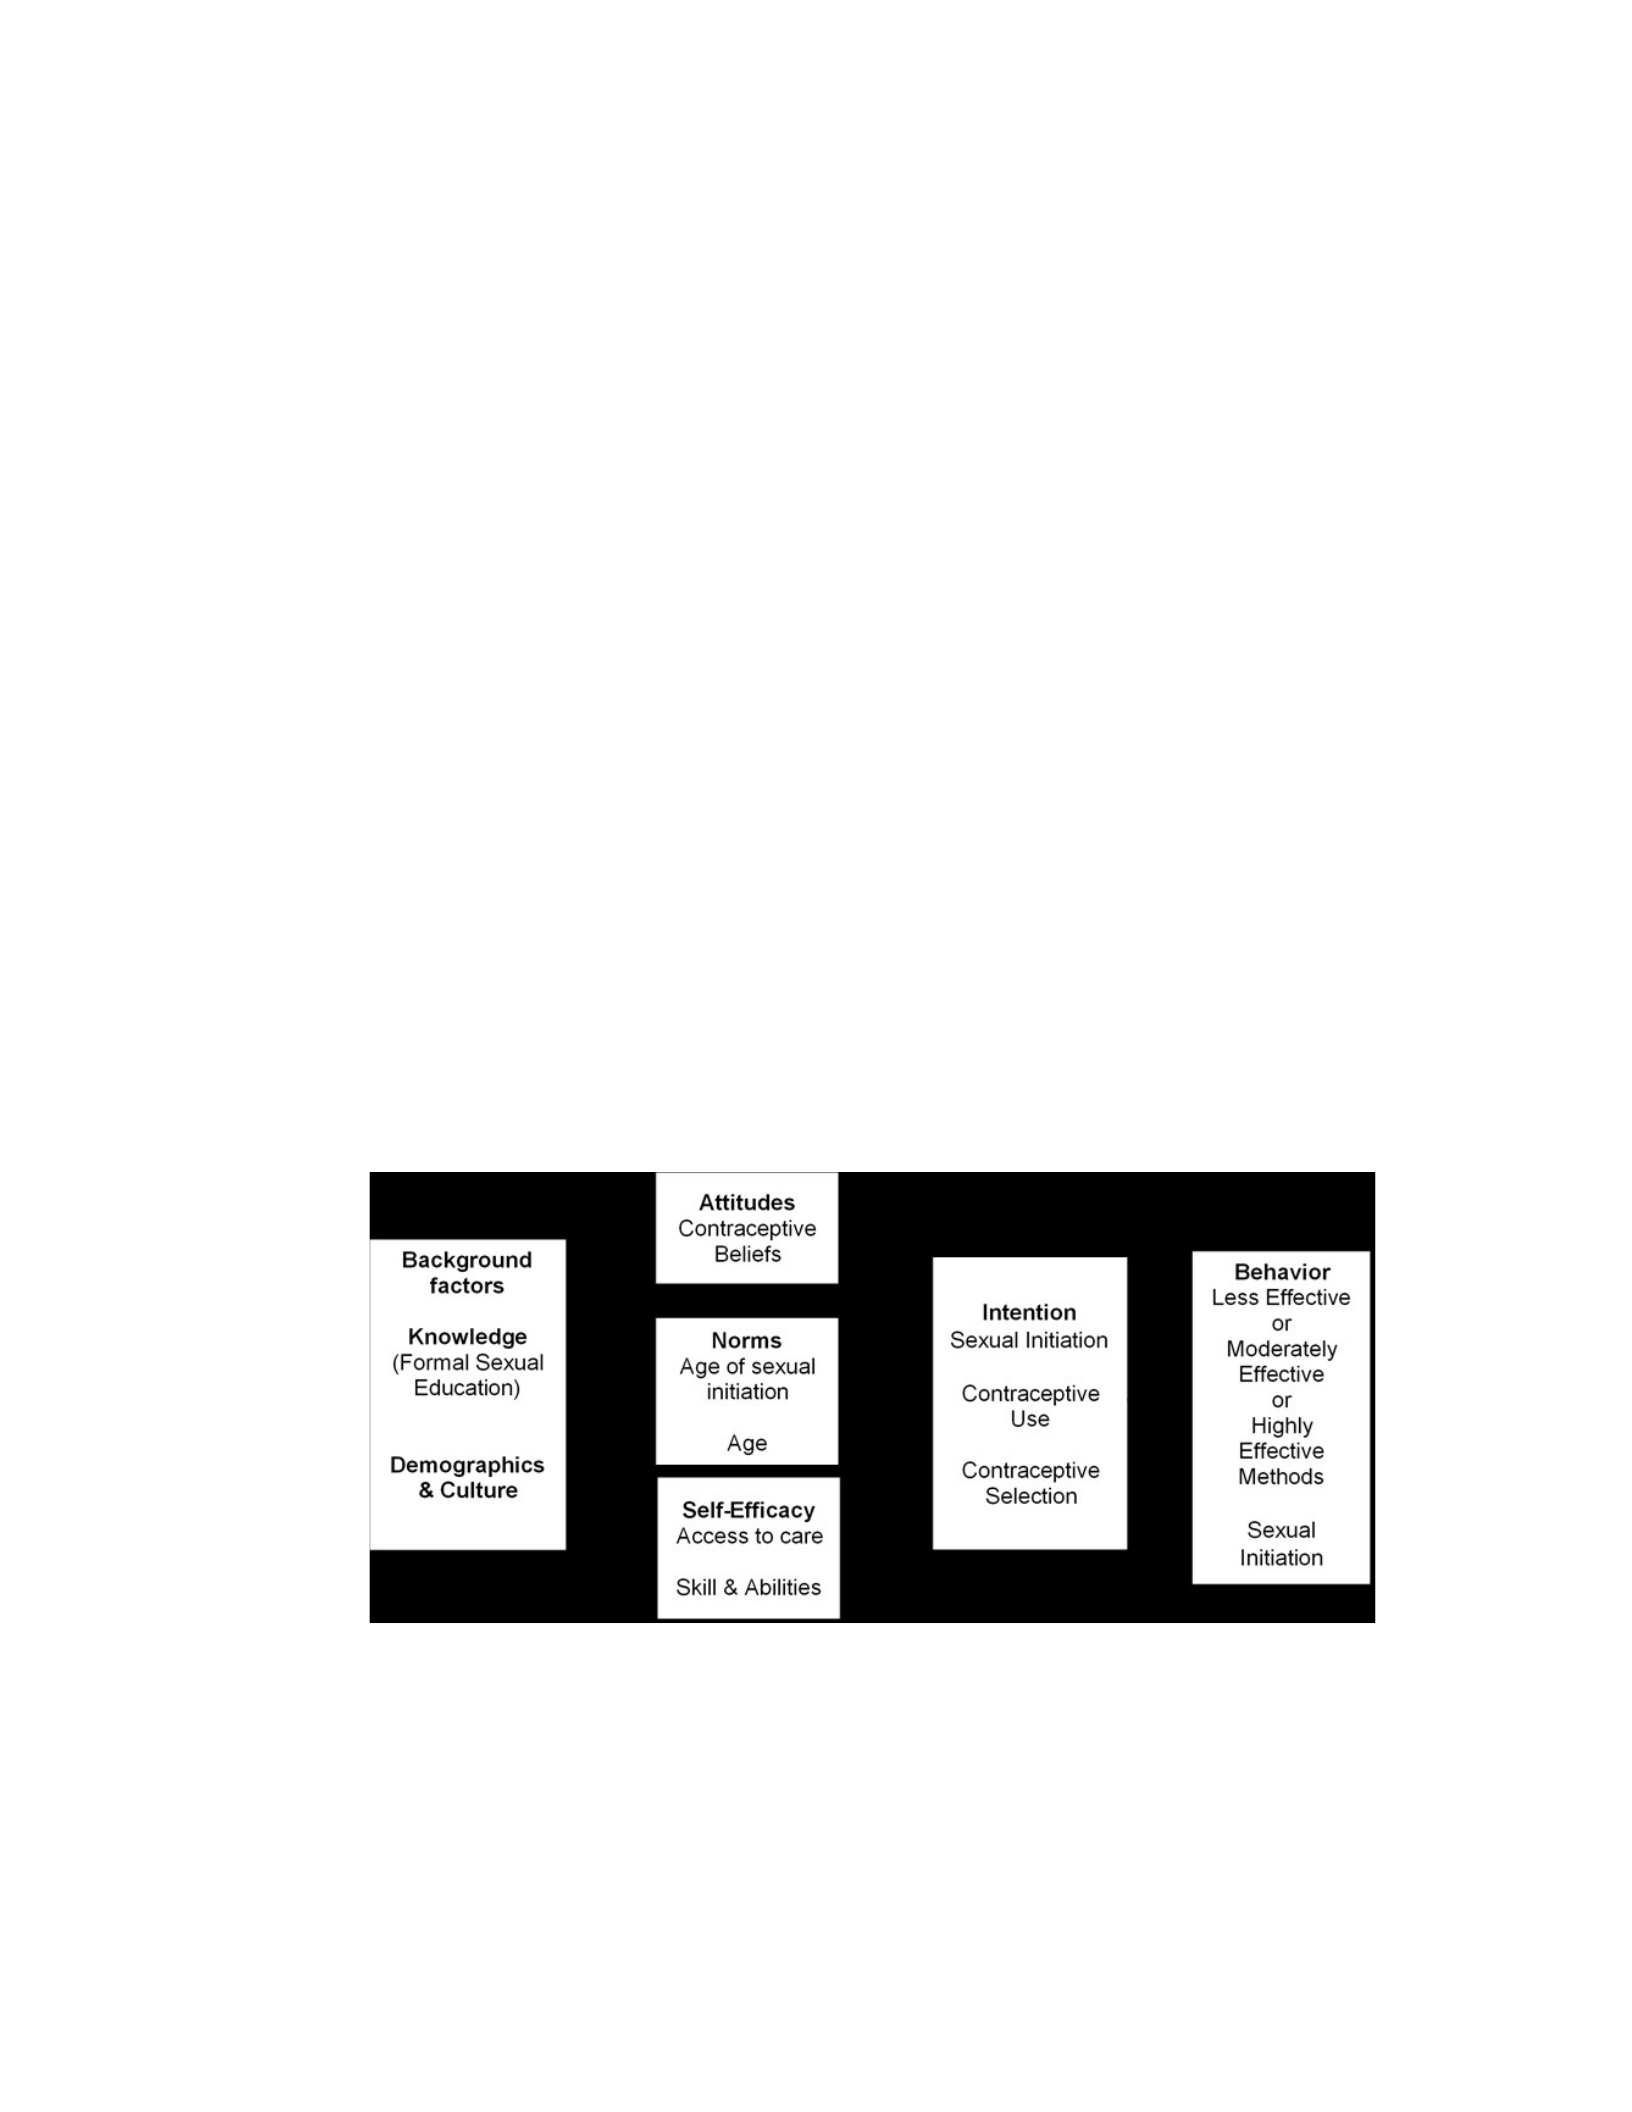
that is the focus of this study. For this study, barrier methods including condoms,
diaphragms, sponges, and spermicides are classified as less effective, with hormonal
methods including oral contraceptives, patch, ring, and injectables classified as
moderately effective (Dehlendorf, Kimport, Levy, & Steinauer, 2014). IUDs, implants,
and sterilization, male or female, are classified as highly effective (Dehlendorf et al.,
2014).
A behavior involves an action directed at a target or performed based on context
within a timeframe (Fishbein, 2008). For this study, I described and defined sexual
initiation and contraceptive use and selection (actions) based on sexual initiation and the
selection of LECMs, MECMs, and HECMs (targets), during vaginal intercourse
(context), within the past 12 months (timeframe; see Figure 1).
Figure 1. Conceptual framework of 2015–2017 NSFG variables. Adapted from “A
reasoned action approach to health promotion” by M. Fishbein, 2008, Medical Decision
Making, 28(6), 834–844.

13
Nature of Study
The NSFG provides the most comprehensive and nationally representative
assessment of reproductive health in the United States. The NSFG gathers information on
family life, cohabitation, marriage and divorce, pregnancy, and infertility, use of
contraception, medical care, and general and reproductive health. NSFG participants were
civilian noninstitutionalized individuals who were 15 to 49 years of age in the United
States. The NSFG is a continuous, computer-assisted survey used to measure
reproductive health status to determine the need for and effectiveness of health education
programs and provide data on American families.
The 2015–2017 data set includes responses collected from 10,094 participants, of
which 5,554 were women (CDC, 2019, 2019c). I selected the NSFG as the secondary
data set for this study due to its oversampling of African American women and
individuals aged 15–24 (CDC, 2019b, 2019c). For this study, I analyzed data from the
2015–2017 NSFG to evaluate the extent to which FSHE (knowledge; main independent
variable) influences sexual initiation (dependent variable) and the selection of LECMs,
MECMs, and HECMs (dependent variables) among African American women aged 18–
24 who have sex with men. I analyzed FSHE, sexual initiation, and contraceptive use and
section data among African American women aged 18–24 who have sex with men from
the NSFG via descriptive statistics, logistic regression, and multinomial logistic
regression.

Definition of Terms
The literature uses various terms to describe African American young women and
their knowledge, attitudes, and beliefs involving FSHE, sexual initiation, and
contraceptive selection and use.
Abstinence-centered sexual health education (ACSHE): A form of education
which involves teaching abstinence until marriage as the only morally acceptable option
and the only way to prevent premarital pregnancy and STIs (Boyer, 2018).
Abstinence-plus sexual health education (APSHE): A form of education that
stresses abstinence as the best way to prevent pregnancy and STIs but includes
information about contraceptives, including condoms (Boyer, 2018).
Behavioral background/distal factors: Demographic, economic, personality,
attitudinal, and other individual factors that play a role in shaping beliefs and behaviors
(Fishbein, 2008).
Behavioral beliefs: Attitudes, including beliefs and feelings about behaviors and
values attached to outcomes of behaviors (Fishbein, 2008).
Behavioral intention: Readiness to engage in a particular behavior (Fishbein,
2008).
Comprehensive sexual health education (CSHE): A form of education that
involves teaching abstinence as the best method for preventing STIs and unintended
pregnancy; it also covers condoms and other contraceptive methods with demonstrations
(Boyer, 2018).

15
Emerging adulthood: A distinct period marked by exploration, development of
independence, and personal decision-making. During this period, individuals make key
decisions regarding romantic and sexual relations, which are heavily influenced by social
norms (Olmstead, Koon, Puhlman, Pasley, & Fincham, 2013).
Highly effective contraceptive methods (HECM): IUDs and hormonal implants
(Dehlendorf et al., 2014).
Less effective contraceptive methods (LECM): Condoms, diaphragms, sponges,
and spermicides, including foam and suppositories (Dehlendorf et al., 2014).
Moderately effective contraceptive methods (MECM): Hormonal methods,
including oral contraceptives, patches, rings, and injectables (Dehlendorf et al., 2014).
Mistimed pregnancy: What a woman experiences if conception occurs sooner than
intended (Levi & Quang Dau, 2011).
Normative beliefs: Subjective and social norms resulting from behavior approval
or disapproval and motivation to comply with beliefs (Fishbein, 2008).
Perceived behavior control/Self-efficacy: Perceptions regarding the ability to
perform a behavior outside of individual control. This includes external factors such as
social support and availability of resources, including affordability and access, as well as
internal factors such as skill/availability and self-efficacy (Fishbein, 2008; Nisson & Earl,
2016).
Permanent contraceptive methods: These methods include tubal ligation and
vasectomy (Tibaijuka et al., 2017).

Reasoned action approach (RAA): Encompasses the theory of reasoned action
(TRA) and planned behavior (TPB) to identify personal, social, and control-related
factors that impact behavior (Hagger et al., 2018).
Sexual initiation: The first sexual experience typically defined as the age of first
vaginal intercourse. (Goldberg & Halpern, 2017).
Short-acting contraceptives: These include oral contraceptive pills, condoms,
spermicides, and injectable hormones.
Unintended pregnancy: A pregnancy that is not planned (Levi & Quang Dau,
2011).
Unwanted pregnancy: A pregnancy experienced by a woman who has no desire to
become pregnant. (Levi & Quang Dau, 2011).
Vicarious experiences: Stories of close family and friends that are valued as if
they are one’s own.
Volitional control: How an individual exercises control over behavior (Fishbein,
2008).
Scope and Delimitations
This research involved investigating possible associations between African
American young women’s exposure to FSHE, sexual initiation, and their selection of
LECMs, MECMs, and HECMs. I selected the NSFG to address this area of research as it
provides information on a national probability sample of civilian noninstitutionalized
women between 15 and 49 years of old. It also provides information on family life,

17
cohabitation, marriage and divorce, pregnancy, and infertility, use of contraception,
medical care, and general and reproductive health. This study only included self-reported,
sexually active African American women aged 18 to 24 who have sex with men and
received FSHE.
Assumptions and Limitations
The purpose of this quantitative cross-sectional analysis of the 2015–2017 NSFG
was to explore the receipt of FSHE and the impact it may have on sexual initiation and
contraceptive use and selection among African American women aged 18–24 who have
sex with men. The NSFG provides general and reproductive health information on a
national probability sample of civilian, noninstitutionalized women age 15 to 49. As such,
when weighted to reflect the United States female population at the interviewing
midpoint, generalizations for the U.S. population may be made (CDC, 2019b, 2019c).
A limitation of this research may be possible non-sampling errors due to the cross-
sectional nature of the NSFG and primary data collection. As such, I could not correlate
the extent to which knowledge impacts contraceptive selection, nor can causal inferences
be drawn from these cross-sectional data. Another limitation of this study involves using
self-reported data, which is subject to participant recall and interviewer biases and over-
and under-reporting. The administration of the majority of the NSFG responses occurred
via audio computer-assisted self-interviewing (ACASI) to reduce limitations and biases
(CDC, 2019b, 2019c).

The sample size was also a limitation of this study. Although oversampling of the
study population occurred to include more African American women, the sample size
was still small; only 1,355 female interviews out of 5,554 were with non-Hispanic Black
women. Another limitation involved the sample size for this study, which included a
subsample from the NSFG containing 499 sexually active, African American women
aged 18–24 who have sex with men. Data cleaning yielded a final sample size of 242
sexually active, African American women aged 18–24 who have sex with men. This
small sample size highlights the need for more robust and targeted studies among African
American women instead of limited qualitative and small studies focusing on nonuse or
large surveys providing percentages of African American women respondents (Mosher et
al., 2015).
Access to data needed to complete this study was another limitation. The NSFG
includes a restricted variable, REGION, that identifies a respondent’s region of residence.
The NSFG website listed the REGION variable as available free of charge upon written
request via encrypted email and confidentiality forms. I followed this procedure but was
informed that access to the REGION variable changed from free to a fee-based model
with limited access at secure onsite facilities, which made the inclusion of this variable
cost-prohibitive. The REGION variable was a crucial part of my initially proposed study
as FSHE requirements vary by state and region. Currently, 24 states and the District of
Columbia mandate sex education, and only 13 require that instruction be medically
accurate (Guttmacher Institute, 2019). Eight states require that instruction be culturally

19
competent and not biased against any race, sex, or ethnicity, and two states prohibit
promoting religion (Guttmacher Institute, 2019). Twenty-seven states require that
abstinence be stressed, 10 states required that it be covered, and only 18 states and the
District of Columbia require information on contraception (Guttmacher Institute, 2019).
FSHE in southern states overwhelmingly requires that abstinence be stressed or covered
compared to other regions. The south comprises states with historically restrictive
reproductive freedom and justice issues, including eugenics, that do not require FSHE to
be culturally competent or non-biased.
Significance
African American women may receive lower quality family planning care,
contributing to disparities in contraceptive use (Craig et al., 2014). African American
young women report earlier sexual initiation, use LECMs, and are more likely to
experience an unwanted or mistimed pregnancy compared to their peers (Golden et al.,
2016; Lanier et al., 2018; Moilanen et al., 2018). Unintended pregnancy can lead to
significant emotional, social, health, and financial complications, which may perpetuate
cycles of disadvantages experienced by vulnerable populations, especially involving
racial disparities in morbidity and mortality later in life. Bourke et al. (2014) found that
CSHE may have a protective influence on early sexual initiation and unintended
pregnancy. Increasing access to CSHE, which highlights modern contraceptive methods,
may raise the age of sexual initiation, and reduce factors that lead to unintended
pregnancy.

The results found from this study may lead to positive social change by providing
sexual health educators and public health practitioners with an understanding of the
impact of FSHE on sexual initiation and contraceptive use and selection among African
American young women who have sex with men. Their increased understanding of the
impact of FSHE may help sexual health educators, and public health practitioners provide
African American young women with knowledge and skills needed to delay sexual
initiation and consistently and properly use preference and intention matched
contraceptive methods. African American young women may apply knowledge and skills
to prevent unintended pregnancy and decrease adverse maternal and child public health
outcomes. Doing so may positively impact African American young women and
children's socioeconomic status, which may lead to improved associated social,
educational, and public health outcomes for both populations.
Summary
Despite a national decline in pregnancy rates, unintended pregnancies in African
American young women remain high and are a public health concern. Even with recent
contraceptive research contributions, information involving selection among African
American young women has not been fully determined. Despite LARC methods being
more cost effective, efficient, and not requiring strict adherence compared to more
common short-acting contraceptives, few young adult women use them (Rubin et al.,
2016). Usage is low in African American young women, which may be due to medical
mistrust resulting from historical reproductive and medical abuse (Jackson et al., 2016).

21
Underuse may be due to misinformation and misperceptions regarding contraceptive
efficacy, side effects, impact on future fertility, social support of contraceptive use,
pregnancy ambivalence, and underestimating pregnancy risk (Craig et al., 2014).
Understanding contraceptive selection among African American young women
may assist sexual health educators and public health practitioners with a better
understanding of the impact of FSHE on contraceptive use and selection and sexual
initiation among African American young women. Results from this study may lead to
positive social change by providing African American young women with knowledge and
skills needed to delay sexual initiation and consistently and correctly use preference and
intention matched methods and reduce the occurrence of unplanned pregnancies in this
population. This information may be used to improve the provision of culturally
competent services, such as sexuality and reproductive education, family planning, and
contraceptive counseling, which may increase selection and consistent use of
contraceptive methods, reduce usage failures, and improve birth-related outcomes.
Provided in Chapter 2 is a review of the literature regarding FSHE, knowledge,
attitudes, and beliefs involving contraceptive use and selection and sexual initiation
among African American young women. Provided in Chapter 3 are details regarding how
data from the NSFG was used to investigate the extent to which knowledge gained
through FSHE impacts sexual initiation and contraceptive use and selection among
African American young women who have sex with men. Presented and interpreted in

Chapter 4 are the results of the statistical analysis techniques discussed in Chapter 3. In
Chapter 5, the study findings are compared to existing empirical literature, and
implications and proposed solutions are discussed.
Chapter 2: Literature Review
Introduction
Unintended pregnancy is associated with adverse emotional, social, economic, and
health outcomes, making it a substantial public health concern. Unintended pregnancy
may lead to disparities in morbidity and mortality due to delayed prenatal care, reduced
breastfeeding, depression, delivery of infants with low birth weight or birth defects, as
well as reduced average income compared to other women (Carter et al., 2013; James &
Rashid, 2013; USDHHS 2019). Infants born due to unintended pregnancies experience
increased risks of poor mental, physical, and behavioral health in adolescence and lower
educational attainment compared to Caucasian infants (James & Rashid, 2013; USDHHS,
2019).
African American women aged 18–24 are at higher risk for unintended pregnancy
due to non-use, inconsistent, or improper use of contraception, as well as failure to use
dual contraceptive methods (Craig et al., 2014). These are topics covered during FSHE.
The purpose of this study was to investigate the extent to which knowledge gained
through FSHE impacts sexual initiation and contraceptive use and selection among
African American women aged 18–24 in the United States who have sex with men. This
information may be used to increase the provision of culturally competent sexuality and

23
reproductive education, family planning, and contraceptive counseling, which may
increase the selection and consistent use of contraceptive methods. This information may
also reduce contraceptive usage failures, raise the age of sexual initiation, and improve
birth related outcomes.
This chapter reviews literature involving FSHE, contraceptive knowledge, beliefs,
decision-making and selection, unintended pregnancy, social and perceived norms, and
sexual initiation associated with African American young. Also, I discuss the RAA,
which successfully predicts and explains increased consistent contraceptive use.
Literature Search Strategy
I conducted a digital literature search through PUBMED, ProQuest Central,
SAGE Journals, and ScienceDirect databases using the following search terms: formal
sexual health education, abstinence-centered, abstinence-plus, and comprehensive sexual
health education, eugenics and historical reproductive justice, contraceptive knowledge,
beliefs, and attitudes, sexual initiation barriers to contraceptive use and access, condoms
and other contraceptives used among teens, young adults, and African American,
perceived and actual contraceptive side effects, and contraceptive social norms. I also
searched for unintended pregnancy, mistimed pregnancy, unwanted pregnancy, older teen
pregnancies, young adult or college pregnancies, young mother, and birth outcomes.
Theoretical Foundation: Reasoned Action Approach The RAA
drove this investigation regarding the extent to which knowledge gained through FSHE
impacts sexual initiation and contraceptive use and selection among African American

women aged 18–24 in the United States who have sex with men. The RAA identifies
personal, social, and control related factors that impact behavior. The RAA integrates
factors from the theory of reasoned action (TRA) and planned behavior (TPB),
focusing on individual motivational factors as determinants of behavior. The TRA and
TPB assume that the best predictor of behavior is intention determined by attitudes and
social norms (Hagger et al., 2018). The TPB includes an additional factor, perceived
control over one’s ability to perform the behavior. Both frameworks have been
successful used by previous researchers to investigate behavioral beliefs such as
attitudes, intentions, and normative beliefs, including vicarious experiences and
subjective norms and their influence on intention (Tyson, Covey, & Rosenthal, 2014).
The TRA asserts that the most important determinant of behavior is behavioral
intention. Through learning, individuals form behavioral beliefs and attitudes. Through
experiences and perceived normative beliefs, intentions are influenced, and individual
behaviors are formed (Fishbein, 2008). Intentions are viewed as readiness to engage in a
behavior (Fishbein, 2008). Attitudes are beliefs and feelings about behaviors and the
values attached to the outcomes of those behaviors. Normative beliefs are subjective and
social norms, including behavior approval or disapproval and motivation to comply with
these beliefs. The TRA involves considering the role that demographic, economic,
personality, attitudinal, and individual factors play in shaping beliefs and behaviors
(Fishbein, 2008). These factors and knowledge are considered background/distal factors
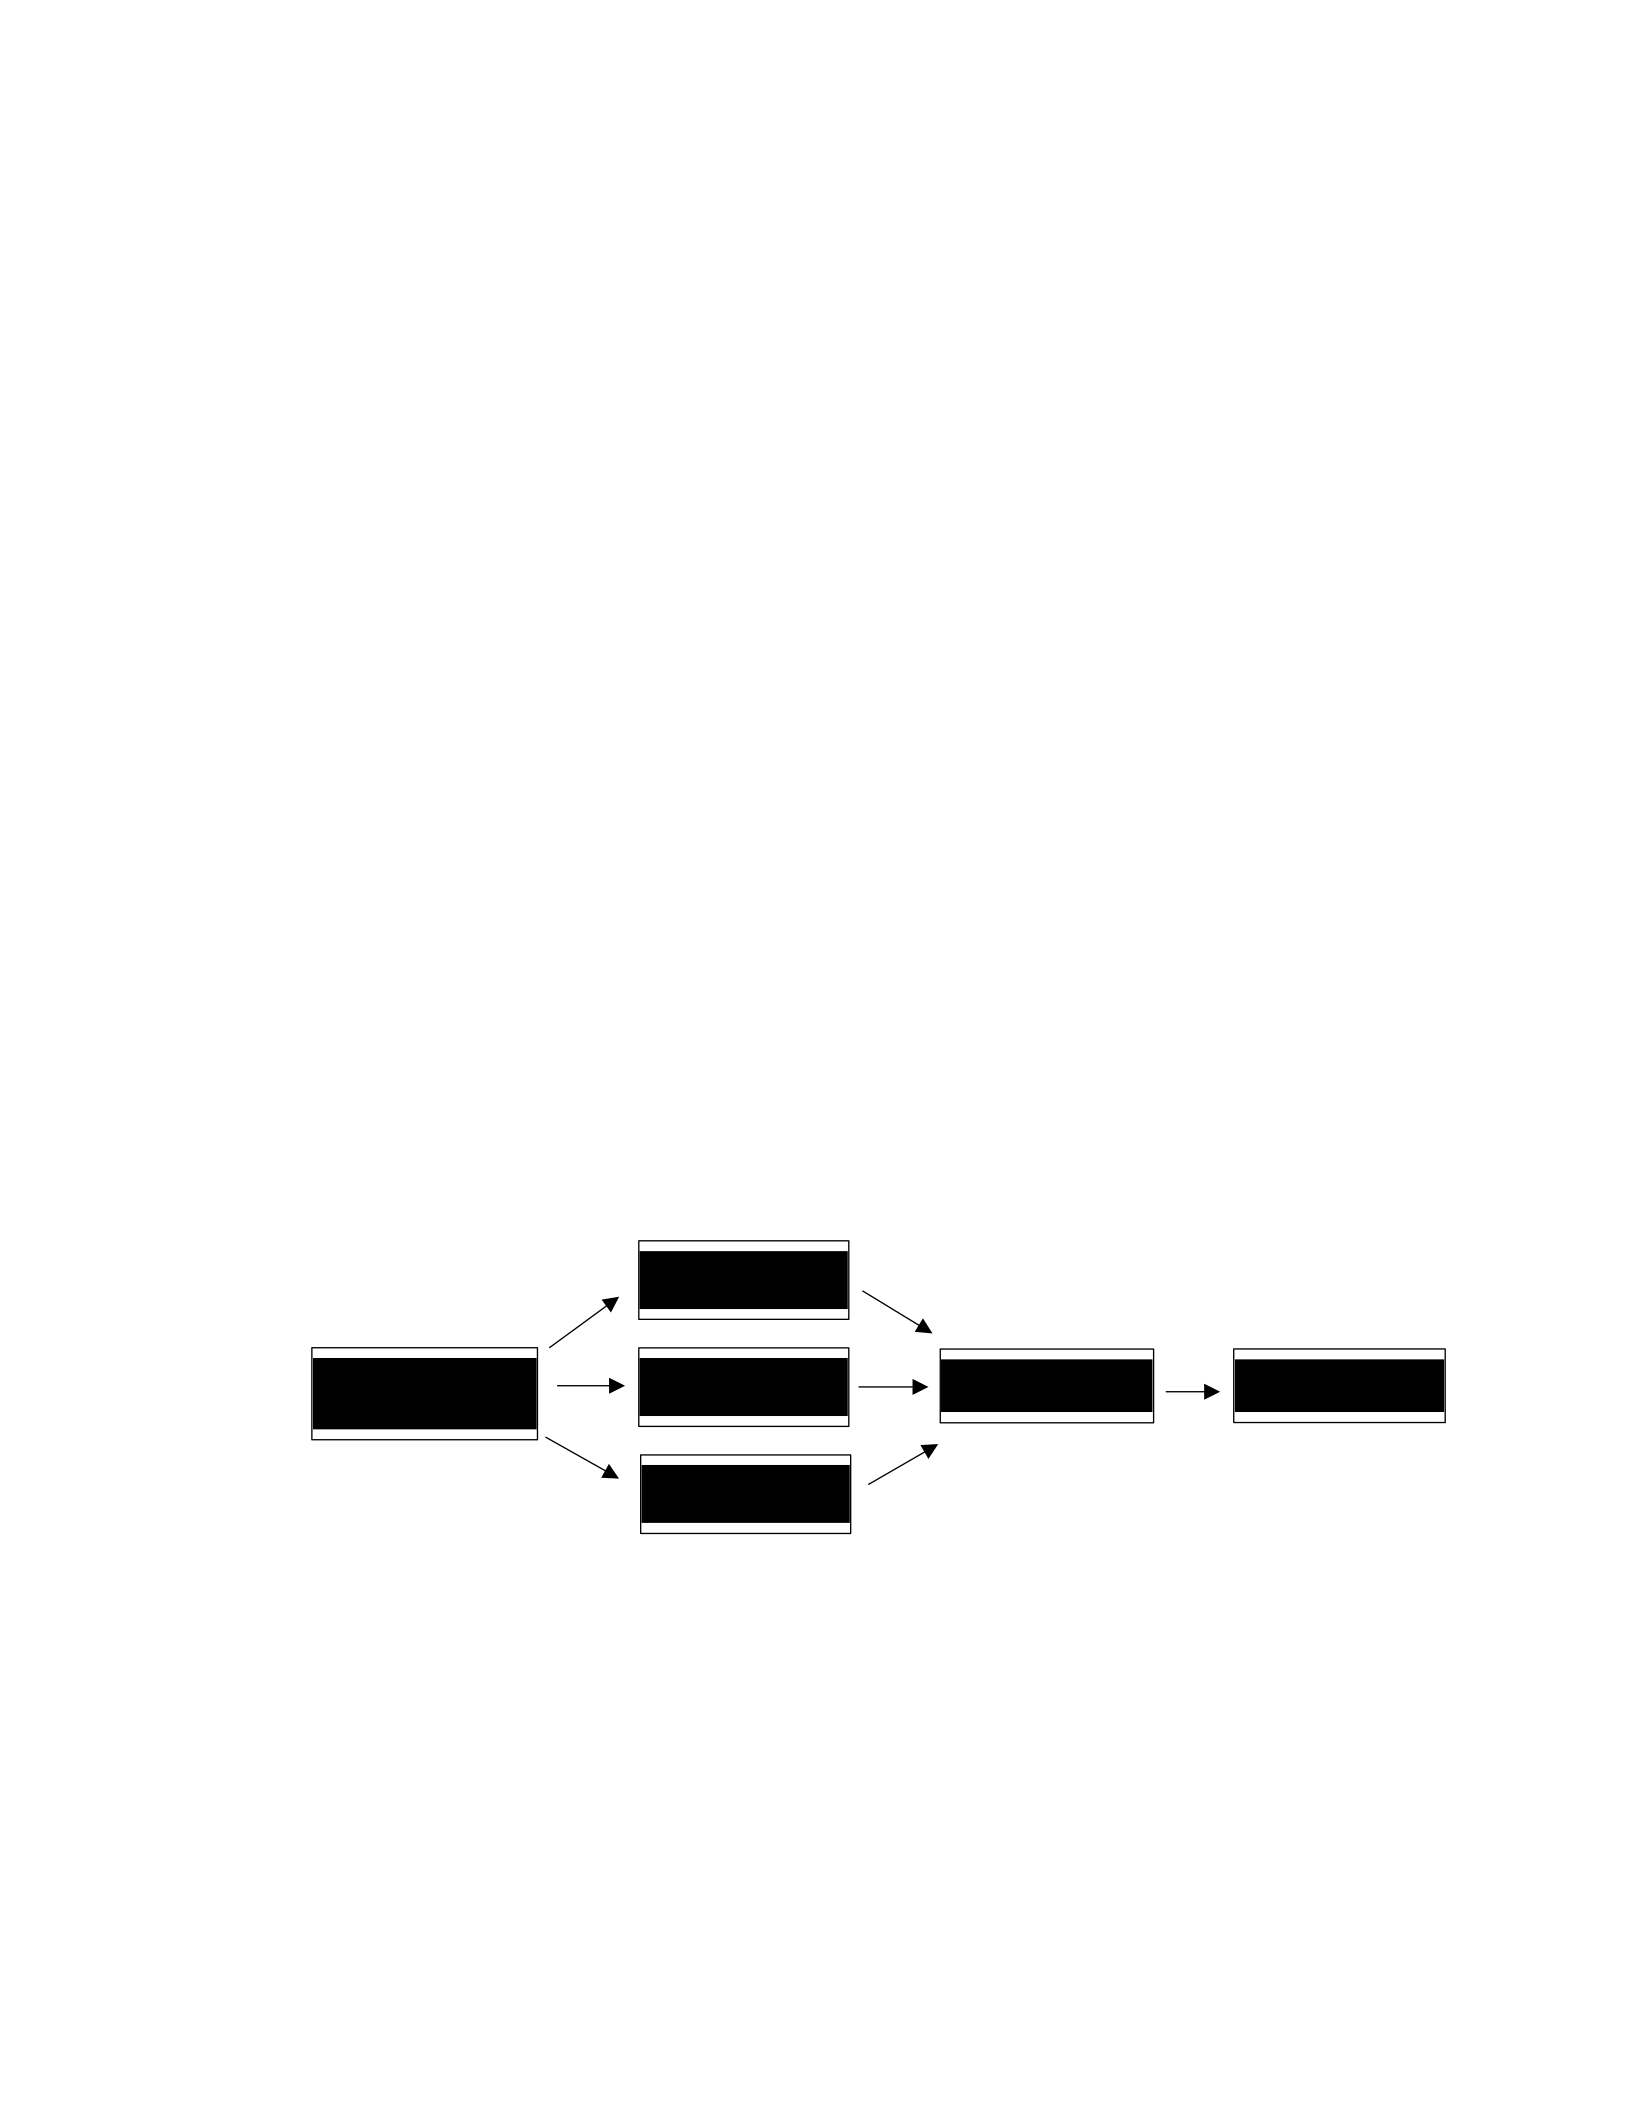
25
that may influence behavioral or normative beliefs through underlying attitudes and
norms.
The ability to which the TRA can explain behavior depends upon volitional
control. The TPB expounds on TRA factors by suggesting that along with attitude toward
the behavior and subjective norms, perceived behavior control/self-efficacy influences
intention. The TPB is widely used when investigating sexual behaviors as it predicts
behavioral intentions influenced by attitudes, norms, and perceived behavioral control.
Behavior control is a person’s perception regarding his or her ability to perform a
behavior that may be outside of his or her control. Control beliefs include external factors
such as social support and availability of resources, including affordability and access, as
well as internal factors such as skill/availability and self-efficacy.
For this research, I used the RAA, which combines TRA and TBP factors most
successful in impacting behavior (see Figure 2).
Figure 2. Model of a RAA. Reproduced from “A reasoned action approach to health
promotion” by M. Fishbein, 2008, Medical Decision Making, 28(6), 834–844.
Attitudes
Background factors Norms Intention Behavior
Self-Efficacy

Reasoned Action Approach and Contraceptive Selection and Use
According to Hoopes, Gilmore, Cady, Akers, and Ahrens (2016), five key themes
influence contraceptive choices: (a) preferences regarding contraceptive characteristics,
(b) contraceptive knowledge gained from peers, family, or health professionals; (c) gaps
in contraceptive knowledge, (d) preferences for effective or long-acting contraceptives,
and (e) barriers and support including partner approval, social norms, and health care
environment. These themes coincide with the RAA factors that focus on attitudes, social
norms, perceived behavioral control, or self-efficacy. Interventions utilizing the RAA
demonstrate that changing attitudes and subjective norms impact intentions to use
contraceptives, leading to behavior change (Dippel, Hanson, McMahon, Griese, &
Kenyon, 2017). In this study, the RAA lent insight into the attitudes, norms, and
selfefficacy associated with contraception intention and decision-making.
Attitudes toward contraceptive behavior include beliefs about benefits or
consequences of performing the behavior, often influenced by knowledge. Attitudes
regarding why young women do not use or discontinue use of contraceptive methods
involve concerns about weight gain, acne, impact on menstruation, invasiveness, and side
effects (Marshall, Kandahari, & Raine-Bennett, 2018). Attitudes that lead to
contraceptive use include ease of use, fewer side effects, low cost, and easy access.
Knowledge shapes contraceptive attitudes (Guzzo & Hayford, 2018). Racial and ethnic
disparities involving contraceptive knowledge exist with associations shown between less
knowledge and less contraceptive use. Not having CSHE is associated with use of

27
LECMs and increased unintended pregnancy (Kim et al., 2016). Teal and Romer (2013)
found that 70% had not heard of LARCs in a multiethnic cohort of young women.
Bachorik et al. (2015) found that 40% of young women were familiar with contraceptive
implants. Misconceptions involving LARCs remain a factor in use disparities among
African American young women. Common misconceptions about LARCs include the
impact on future fertility, overestimating associated risk, underestimating oral
contraceptive risk, and overestimating oral contraceptive effectiveness (Sundstrom,
Baker-Whitcomb, & DeMaria, 2015).
Perceived social norms toward sexuality, contraceptive use, and pregnancy are
formed based on familial experiences, which vary by race. African American women are
exposed to higher teen and single parenthood rates, earlier sexual initiation, and use
contraceptives less effectively (Barber et al., 2015). Barber et al. (2015) suggested that
exposure to these factors may cause cognitive dissonance and perpetuate these behaviors.
Anderson, Steinauer, Valenete, Koblentz, and Dehlendorf (2014) found that among
diverse women, negative information regarding LARCs learned from conversations with
female friends and family members and television commercials impacted decision
making. Oral contraceptives are reported as the most acceptable form of contraception
and LARCs, including intrauterine devices, are rarely used (Pritt, Norris, & Berlan,
2017). African American women who perceive negative peer norms surrounding
contraceptive use are more likely to have inconsistent contraceptive usage and use
LECMs (Crosby et al., 2013). Cohen, Sheeder, Kane, and Teal (2017) suggested that
knowledge regarding contraceptive methods alone is insufficient to increase use since

African American women valued anecdotal information just as favorably as factual
information. As such, the stronger predictor for contraceptive method choice in their
study was knowing someone who used, liked, or disliked a particular method. Marshall et
al. (2018) also noted the importance of experiential information from friends and family
in contraceptive decision-making. They described healthcare providers as both trusted
and potentially biased sources of factual only information and noted that there is often
skepticism regarding providers’ ability to provide unbiased reproductive
recommendations. In some instances, participants reported that they made contraceptive
decisions without seeking social support, preferring to learn from personal negative
contraceptive experiences instead of relying on the experiences of their social
communities (Paterno, Hayat, Wenzel, & Campbell, 2017). Anecdotal information and
personal experiences might supersede formal education for African American young
women (Carter et al., 2012).
Self-efficacy involving contraceptive behaviors includes the availability of
resources, including affordability and access, and the skill needed to perform the behavior
(Fishbein, 2008; Nisson & Earl, 2016). Uninsured and underinsured women are more
likely not to use contraception or to use LECMs and be at increased risk for unintended
pregnancy than those with private insurance (Kim et al., 2016). Young women not
covered by a parent’s insurance plan might opt out of electing insurance coverage and
remain uninsured (Pritt et al., 2017). Insured women might not be aware of the benefits
centered around contraceptive costs (Pritt et al., 2017). The costs of LECMs might

29
influence clinics’ ability to stock them, which could affect patients’ timely access to
contraception (Pritt et al., 2017). Reproductive trends in contraceptive use among African
American women may be impacted by a reproductive history of medical and reproductive
abuse (Jackson et al., 2016). Young women, especially African Americans, may be at risk
of not receiving high-quality family planning care (Dehlendorf et al., 2014). African
American women report experiencing implicit and explicit bias in the form of feeling
coerced to start contraceptive use earlier than desired, written prescriptions provided
without request or consent, refusal to remove implanted methods when requested (Gomez
& Wapman, 2017). They also report feeling as if they could not turn down provider
recommendations and being steered toward more long-acting methods without
considering their reproductive preferences and priorities (Gomez & Wapman, 2017).
Contraceptive dissatisfaction and lack of knowledge regarding alternatives may also
contribute to nonuse or incorrect use of current contraceptive methods (Kornides et al.,
2015). The RAA has been used successfully to investigate self-efficacy associated with
contraceptive use and partner reaction, especially regarding contraception negotiation
(Villarruel et al., 2004). CSHE increases self-efficacy and the skill needed to select and
use more effective contraception.
Conceptual Framework
The purpose of this study was to use a RAA to investigate the extent to which
knowledge gained through FSHE impacts sexual initiation and contraceptive use and
selection among African American women aged 18–24 who have sex with men. The first

step in a RAA is to describe and define the behaviors of interest. The behavior that was
the focus of this study is contraceptive methods selection by African American young
women. For this study, barrier methods including condoms, diaphragms, sponges, and
spermicides have been classified as less effective, with hormonal methods including oral
contraceptives, the patch, the vaginal ring, and injectables classified as moderately
effective (Dehlendorf et al., 2014). IUDs, implants, and sterilization have been classified
as highly effective (Dehlendorf et al., 2014).
In the RAA, behavior involves an action directed at a target, performed based on
context, within a timeframe (Fishbein, 2008). For this study, these constructs are
described and defined as contraceptive selection (action) based on the selection LECMs,
MECMs, and HECMs (target), during vaginal intercourse (context), within the past 12
months (time; see Figure 1).
Literature Review
Formal Sexual Health Education
FSHE is comprised of an evidence based curriculum delivered in a school or
healthcare setting. FSHE may be based on different methods, including an
abstinencecentered, abstinence-plus, or comprehensive approach. ACSHE, often referred
to as sexual risk avoidance programs (SRAP), teaches abstinence until marriage as the
only morally acceptable option before marriage (Boyer, 2018). Participants are taught
that abstinence is the only way certain to prevent premarital pregnancy and STIs and that
sex within a monogamous relationship in the context of marriage is the expected standard

31
(Boyer, 2018). ACSHE programs also teach that sexual activity outside of marriage is
likely to have harmful psychological and physical effects and impact independence
(Boyer, 2018). ACSHE programs do not include demonstrations, simulations, or the
distribution of contraceptive devices (Boyer, 2018). ACSHE programs typically fail to
provide education and skill-building on critical topics such as healthy relationships,
communication, and consent (Boyer, 2018).
APSHE stresses abstinence as the best way to prevent pregnancy and sexually
transmitted infections but emphasizes safe sex practices, healthy relationships, and
lifestyles by including information about contraception and condoms. CSHE teaches
abstinence as the best method for preventing STIs and unintended pregnancy but also
teaches participants about condoms and other contraceptive methods with demonstrations
(Boyer, 2018). It helps young people explore their values, goals, and options by teaching
interpersonal and communication skills (Boyer, 2018).
Despite concerns, there is no evidence to support that receipt of CSHE is
associated with an earlier sexual initiation, increased risk-taking, or poorer sexual
reproductive health outcomes (Lindberg & Maddow-Zimet, 2012). CSHE, which occurs
before sexual initiation, leads to delayed onset of sexual initiation, greater use of more
effective contraception, especially at the first sexual encounter, and healthier sexual
relationships (Jaramillo, Buhi, Elder, & Corliss, 2017; Lindberg & Maddow-Zimet,
2012). ACSHE does not have a significant impact on sexual initiation or sexual behaviors
and may place young people at increased likelihood of pregnancy and STIs once they

become sexually active by overlooking or downplaying the benefits of contraception
(Boyer, 2018). ACSHE also fails to meet the needs of young people who are already
sexually active, withholding potentially lifesaving information (Boyer, 2018). ACSHE
also perpetuates discrimination and stigmatizes sex, promoting fear, guilt, and shame
around sex (Boyer, 2018). It also ignores systemic biases such as racism, inequality,
discrimination, and trauma, which may impact the sexual health of African American
women (Boyer, 2018). Public health professionals widely reject ACSHE and SRAP
(Santelli et al., 2017).
The goal of FSHE is to prepare young adults to be sexually healthy (Santelli et al.,
2017). Before 2008, federally funded educational programs focused solely on ACSHE
programs, prohibiting discussing contraceptive methods, except to emphasize their failure
rates (Jaramillo et al., 2017; Lindberg & Maddow-Zimet, 2012). In 2010, a reduction in
funding for ACSHE occurred, and the Obama Administration increased CSHE (Jaramillo
et al., 2017). The current administration reverted the content of FSHE to ACSHE without
scientific evidence supporting their effectiveness. As such, the requirements for FSHE
vary by state and region. Currently, 24 states and the District of Columbia mandate sex
education, of which only 13 require that instruction be medically accurate (Guttmacher
Institute, 2019). Eight states require that instruction be culturally competent and not
biased against any race, sex, or ethnicity, and two states prohibit promoting religion
(Guttmacher Institute, 2019). Twenty-seven states require that abstinence be stressed, and
10 required that it be covered, while only 18 states and the District of Columbia require

33
information on contraception (Guttmacher Institute, 2019, see Table 1). As noted, Region
3, comprised of southern States, overwhelmingly requires that abstinence be stressed or
covered compared to other regions. There are no states in Region 3, historically known
for restrictive reproductive freedom and justice issues, including eugenics, that require
FSHE that is culturally competent and non-biased.
Racial and ethnic disparities involving contraceptive knowledge exist with an
association shown between less knowledge and less contraceptive use. FSHE, for most, is
received through school based programs, which may not be comprehensive, and often in
the South has moral undertones (Guzzo & Hayford, 2018). Receipt of FSHE was lower
among individuals with lower socioeconomic status, who were African American, and
whose mothers had lower educational attainment (Lindberg & Maddow-Zimet, 2012).
Receipt of FSHE after high school is rare. Therefore, knowledge and attitudes formed
about contraception during adolescence may persist throughout life (Guzzo & Hayford,
2018). This highlights the need for CSHE among African American young women who
have poorer sexual reproductive health outcomes, including higher rates of unintended
pregnancy and STIs (Lindberg & Maddow-Zimet, 2012). Shepherd, Sly, and Girard
(2017) found that African American adolescents who received CSHE had more favorable
attitudes about contraception, demonstrated an increase in consistent contraception usage,
and reported less teen pregnancy and vaginal intercourse, highlighting the importance of
early CSHE.
Table 1

U.S. Census Bureau Regions and Divisions with State FIPS Codes and FSHE
Requirements
United States Census Bureau Regions and Divisions with State FIPS Codes
Regional I: Northeast
States Requirement Codes
Connecticut (09)
Maine (23) MSE, MA, AS, CE
Massachusetts (25)
New Hampshire (33)
New Jersey (34) MSE, MA, CC, AS, CE
New York (36)
Pennsylvania (42)
Rhode Island (44) MSE, MA, CC, AS, CE Vermont
(50) MSE, AC, CE
Region 2: Midwest
States Requirement Codes
Illinois (17) MA, AS, CE Indiana
(18) AS
Iowa (19) MSE, MA, CC
Kansas (20)
Michigan (26) MA, AS
Minnesota (27) MSE, AC Missouri
(29)
Nebraska (31)
North Dakota (38) MSE
Ohio (39) MSE, AS
South Dakota (46)
Wisconsin (55) AS
(table continues)
United States Census Bureau Regions and Divisions with State FIPS Codes
Region 3: South
States Requirement Codes
Alabama (01) AS, CE
Arkansas (05) AS
Delaware (10) MSE, AS, CE
District of Columbia (11) MSE, CE Florida
(12) AS
Georgia (13) MSE, AS
Kentucky (21) MSE, AS
Louisiana (22) AS
Maryland (24) MSE, AC, CE
Mississippi (28) MSE, AS
North Carolina (37) MSE, MA, AS, CE
Oklahoma (40) AS
South Carolina (45) MSE, AS, CE
Tennessee (47) MSE, AS

35
Texas (48) AS
Virginia (51) AC
West Virginia (54) MSE, AC, CE
Region 4: West
States Requirement Codes
Alaska (02)
Arizona (04) AS
California (06) MSE, MA, CC, AC, CE
Colorado (08) MA, CC, AC, CE Hawaii
(15) MSE, MA, AC, CE
Idaho (16)
Montana (30) MSE, AC
Nevada (32) MSE
New Mexico (35) MSE, AC, CE
Oregon (41) MSE, MA, CC, AS, CE
Utah (49) MSE, MA, CC, AS
Washington (53) MA, CC, AS, CE
Wyoming (56) Legend:
Mandated Sex Education (MSE)
Required Medically Accuracy (MA)
Required Culturally Competent and Non-biased instruction (CC)
Abstinence Stressed (AS)
Abstinence Covered (AC)
Required Contraception Education (CE)
Contraceptive Use and Selection
Demographics. Timing and sequencing of experiences across the lifespan are
important as young women make choices based on their experiences. Young women’s
decisions about contraception depend on their life experiences, which are influenced not
only by race but by age (Kusunoki, Barber, Ela, & Bucek, 2016). Women in their late
teens and twenties are in a transition period where they are deciding who they are and
shaping their personalities and beliefs based on familial beliefs, education and
experiences from adolescence, and exploration in a world that is defined by less parental
oversight. For this research, I focused on young adult, African American women aged
18–24.

Women aged 18–19 are late adolescents beginning the transition to adulthood.
Developmental researchers emphasize the importance of this transition as experiences
begin to diverge, which shape adulthood decisions. While some remain at home while
attending college, working, or combining the two, most late adolescents leave home to
attend college or work full-time while living independently (Arnett, 2000). Dating
provides companionship, first loves, and sexual experimentation. Parental supervision
lessens, and there is little normative pressure to marry. Women aged 20–24 are emerging
adults with relationships based on shared values and belief systems, who modify their risk
taking behaviors and make decisions based on future consequences (Arnett, 2000).
Emerging adults have the greatest residential change in any group (Arnett, 2000). While
most continue to live in collegiate residential facilities or independently, some cohabitate
with a romantic partner (Arnett, 2000). Emerging adults reexamine familial beliefs and
form personal beliefs that will shape adulthood (Arnett, 2000). Dating becomes serious,
and the focus shifts to exploring the potential for marriage. While college attendance is at
an all-time high, only 36% of young adults have earned their degrees (U.S. Bureau of
Census, 2016). Many pursue graduate degrees while others begin their occupational path
and possibly marriage and family (Arnett, 2000).
These age groups contracept differently. Contraceptive knowledge is typically
lower, and unintended pregnancies are higher in 18–19 year old women (Wu, Kusunoki,
Ela, & Barber, 2016). Dehlendorf et al. (2014) found that African American women
under 19 years of age were less likely than Caucasians women to use IUDs or implants,

37
while African American women between the ages of 20–24 were slightly more likely to
use IUDs and implants than Caucasians. Additional contraception differences based on
age are discussed in the next section.
Contraception among African American women. Contraception is used to
prevent pregnancy and the interruption of life goals it could cause (Morse & Moos,
2018). For this research, I categorized contraceptive methods based on the World Health
Organization’s effectiveness recommendations. Barrier methods, including condoms,
diaphragms, sponges, and spermicides, are LECMs, and hormonal methods, including
oral contraceptives, the patch, the vaginal ring, and Depo-Provera injections are MECMs.
IUDs, implants, and sterilization are HECMs. LECMs and MECMs offer varying levels
of effectiveness based on method selection and usage patterns. These methods are the
most used due to lower cost, ease of access, and reversibility, with effect wearing off
quickly once use has ceased or shortly after (USDHHS, 2019). LARC methods provide
hormonal or non-hormonal protection for three to 10 years with one application,
depending on the method, and are HECM. These methods have a higher initial cost but
are more cost effective due to the length of protection provided (USDHHS, 2019).
LARCs are reversible, with effects wearing off once use has ceased or shortly after
(USDHHS, 2019). LARCs include hormonal implants that may be intrauterine hormonal
devices or subdermal implants and non-hormonal IUDs. Permanent contraceptive
methods, including tubal ligation and tubal sterilization, are also HECM used to provide
hormone-free, permanent pregnancy prevention.

Despite most young adults believing that pregnancy should be planned (86–94%),
more than 70% of pregnancies among unmarried women aged 18–24 are unplanned and
likely due to nonuse or inconsistent contraceptive use (Kornides et al., 2015). Half of
unintended pregnancies occur among contraceptive users, with 90% of these pregnancies
resulting from inconsistent or incorrect method use rather than method failure (Wong,
2012). Reasons for nonuse or inconsistent contraceptive use include the belief that one
could not get pregnant (32%), lack of preparedness due to unexpected intercourse (20%),
pregnancy ambivalence (18%), lack of partner desire for contraceptive use (16%), and
concern over contraceptive side effects (15%; Kornides et al., 2015). Paterno et al. (2017)
found that among women aged 20–24, 11.4 to 13% used no contraceptive method. This
number was lower among African American participants despite 60% of African
American women aged 18–24 who believed pregnancy planning is important and 80%
who desired to avoid pregnancy (Paterno et al., 2017).
Barber et al. (2015) found that African American young women tolerated male
partner refusal to use condoms because of the scarcity of potential partners. Sexual health
education focused on condom usage as the best option; however, they are only 79–82%
effective due to incorrect use (Logan et al., 2018; USDHHS, 2019). Condoms are most
effective when used in combination with a dual, hormonal contraceptive method,
providing protection from pregnancy and STIs (USDHHS, 2019). Oral pills have also
been the focus of sexual health education as an ideal contraceptive method, which
provides young women with a false sense of protection due to the overestimation of

39
effectiveness (Logan et al., 2018). Many are unaware that contraceptive effectiveness
may be impacted by medication, such as antibiotics, and failure to take the pill at the
same time daily. According to the NSFG, African American women have higher oral pill
discontinuation rates than Caucasian women, which may be due to side effect concerns
(Jackson et al., 2016).
Although LARC use has increased over the past five years, use is still low in
young women despite being one of the most effective forms of pregnancy prevention
(Logan et al., 2018). Fewer than 5% of 15–19 year olds select LARCs as their preferred
contraception method (Coates, Gordan, & Simpson, 2018). LARC use varies by age;
however, with women aged 25–34 using LARCs at nearly double the rate of women aged
15–24 (Logan et al., 2018). Despite this increase, young African American women's
usage remains lower than in other racial/ethnic groups (Logan et al., 2018). Coates et al.
(2018) found that in Alabama and Mississippi, two Region 3 states, only 3.7% to 7% of
15–19 year olds used LARCs. Usage may be due to insufficient knowledge and negative
attitudes and beliefs about LARCs stemming from social norms, the knowledge gained
through vicarious experiences, and knowledge of institutional racism and medical
mistrust (Logan et al., 2018). As LARCs are more expensive than LECMs and MECMs
methods and require insertion by a healthcare provider, the lack of insurance may be a
barrier to use (Logan et al., 2018). However, LARC methods are more effective than
LECMs and MECMs, provide better child spacing, are more cost effective, and their
effectiveness is less dependent on user characteristics (Tibaijuka et al., 2017).

Women prefer methods that do not require procedures, which may stem from fear
based on historical reproductive abuse that perpetuates perceptions of institutional racism
and medical mistrust (Jackson et al., 2016; Logan et al., 2018; Tibaijuka et al., 2017).
Even when women want to avoid pregnancy, their contraceptive behaviors are not
necessarily consistent with their intention (Borreo et al., 2015). Potentially modifiable
factors that may contribute to contraceptive use or inconsistent use among African
Americans are perceived low susceptibility of pregnancy, lack of knowledge regarding
contraceptive options, and misperceptions surrounding contraceptive side effects (Borreo
et al. 2015; Kornides et al., 2015). Previous unprotected intercourse without pregnancy
may lead to subfertility or infertility assumptions and give rise to subsequent
contraceptive nonuse or inconsistent use (Borreo et al., 2015). Compared to Caucasian
and Hispanic women, African American women are more likely to report concerns
regarding side effects of contraceptive methods as their rationale for not using
contraception (Kornides et al. 2015). Few women aged 20–24 use LARCs, such as an
IUD implant and injectable hormonal contraception, which may be due to a lack of
knowledge and misconceptions that these methods may be abortifacients (Kornides et al.,
2015). Contraception use, specifically LARC use, might be increased by providing young
women more information on effectiveness, side effects, affordability, and ease of use
(Kornides et al., 2015).
African Americans rely heavily on social networks for sexual and reproductive
norms and information (Hayford & Guzzo, 2013). The social context of pregnancy

41
includes views of family members or partners, cultural values about pregnancy,
contraception, single parenthood, and life choices resulting from unintended pregnancy
(Kelly, 2014). Low social support during pregnancy is associated with substance use and
abuse, poor nutrition, and lack of exercise (Gray, 2015).
Sexual Initiation
Sexual initiation, considered a critical life transition event, is a significant
milestone towards adulthood as young adults accept increasing responsibility for their
decisions (Goldberg & Halpern, 2017; Moilanen et al., 2018). The mean age of sexual
initiation among American women is approximately 17 years of age, with 15% having
had their first heterosexual vaginal intercourse experience before their 15th birthday
(Guttmacher Institute, 2018; Magnusson, Nield, & Lapane, 2015). African American
young women report earlier sexual initiation and are more likely to experience an
unwanted or mistimed pregnancy than their peers (Moilanen et al., 2018). Current
national norms for the United States consider sexual initiation before age 15 as early,
between 15 and 19 years of age as normative, and after 19 years of age as late (Golden et
al., 2016). Women who experience early sexual initiation are less likely to use
contraception and are prone to an increased risk for depression and lower self-esteem
(Golden et al., 2016; Lanier et al., 2018). Magnusson et al. (2015) found that women with
early sexual initiation also have a higher risk of experiencing multiple unintended
pregnancies compared to women with late sexual initiation.

CSHE may have a protective influence on early sexual initiation (Bourke et al.,
2014). CSHE, grounded in a sex-positive framework, teaches young adults that
consensual sexual behavior can be healthy, normative, and developmentally appropriate
(Bourke et al., 2014; Golden et al., 2016). CSHE equips young adults with the tools
needed to make well-informed and healthy decisions around sexual experiences to reduce
risk and promote healthy development (Golden et al., 2016).
Access to Care
Reproductive trends in contraceptive use among African American women may
be impacted by a reproductive history of medical and reproductive abuse (Jackson et al.,
2016). The United States has a history of social and legislative policies to control the
reproductive health of poor and minority women through forced sterilization (Jackson et
al., 2016). With the introduction of contraceptive implants, many states incentivized or
required usage among women who relied on governmental aid (Jackson et al., 2016).
Combined with historical occurrences such as the Tuskegee experiment, mistrust of
reproductive health practitioners and their recommendations is high. As such, African
American women are more likely than Caucasian women to use LECMs due, in part, to a
desire to preserve reproductive control (Jackson et al., 2016).
Young women, especially those of color, may be at risk of not receiving
highquality family planning care (Dehlendorf et al., 2014). This may contribute to
healthcare disparities, disengagement from healthcare interactions, and perpetuated
institutional mistrust (Gomez & Wapman, 2017). Young women described feelings of

43
being rushed during appointments, not having questions answered and concerns
addressed, and receiving no information or incomplete information regarding the
method’s side effects provided (Gomez & Wapman, 2017). Contraceptive dissatisfaction
and lack of knowledge regarding alternatives may also contribute to nonuse or incorrect
use of current contraception methods (Kornides et al., 2015). Dissatisfaction and lack of
knowledge may stem from family planning healthcare disparities. Implicit and explicit
bias/pressure, experienced during family planning, may influence contraceptive
decisionmaking, and perpetuate reproductive oppression experienced by minority women
(Gomez
& Wapman, 2017).
Effective patient-centered family planning care should account for medical history
and be engaging, nondirective, interactive, and consider patient preferences and priorities
(Gomez & Wapman, 2017). Provider initiated discussions and recommendations
influenced by race, class, age, or feelings of perceived judgment have a long lasting
impact on young women’s confidence in the healthcare system. This doubt or lack of
confidence may influence decisions to seek and receive contraceptive care (Gomez &
Wapman, 2017). Clinicians are more likely to recommend LARCs to low income women
of color compared to their Caucasian counterparts (Gomez & Wapman, 2017). This type
of provider coercion is seen particularly with patients deemed high-risk, despite their
contraceptive preferences (Morse & Moos, 2018). Provider coercion occurs despite
income, with well-educated patients describing feelings of pressure to be compliant,

discomfort with expressing their opinions and views, and the need to accept provider
recommendations (Joseph-Williams, Edwards, & Elwyn, 2014; Sacks, 2017).
Operationalizing Reproductive Health
The NSFG provides the most comprehensive, nationally representative assessment
of reproductive health in the United States. It provides information on family life,
marriage and divorce, pregnancy, infertility, use of contraception, and general and
reproductive health on a nationally representative sample of the civilian,
noninstitutionalized United States population aged 15– to 49 based on voluntary, inperson
computer assisted personal interviewing (CAPI). The NSGF continuously interviews the
U.S. population, annually over 48 weeks (CDC, 2019b, 2019c). The 2015– 2017 data set
includes responses collected from 10,094 participants, of which 5,554 were women
(CDC, 2019b, 2019c). I chose the NSFG as the data set for this study due to its
oversampling of African American women and individuals aged 15–24 (CDC, 2019b,
2019c).
For this study, I used NSFG variables related to receipt of FSHE, type of
contraceptive method selected for vaginal intercourse at sexual initiation and within the
last 12 months, and age of sexual initiation among African American women aged 18–24
who have sex with men. Participants’ receipt of FSHE before 18 years of age is
categorized as received (yes) or not received (not). If participants self-reported FSHE was
received, the responses collected helped determine if education was ACSHE, APSHE, or
CSHE based on coverage of birth control methods, where to get birth control, how to use

45
a condom, and waiting until marriage to have sexual intercourse. The stratification of
these variables' results occurred by age into the standard population age groups into the
age brackets of 18–19 and 20–24 years old.
Operationalizing Unintended Pregnancy
Since 1941, unintended pregnancy has been a marker of reproductive health and
dichotomized as one that was either mistimed or unwanted (Guttmacher Institute, 2018).
Mistimed pregnancies, which account for 27% of pregnancies, are characterized as
pregnancies that were not wanted when they occurred, but pregnancy may be desired in
the future (Guttmacher Institute, 2018). Unwanted pregnancies, which account for 18% of
pregnancies, are characterized as pregnancies that were not wanted when they occurred or
in the future (Guttmacher Institute, 2018). An intended pregnancy is one that was wanted
at the time it occurred or sooner (Guttmacher Institute, 2018). Women who were
indifferent about becoming pregnant are counted as intended pregnancies, so that the
unintended pregnancy rate only includes unambiguously unintended pregnancies
(Guttmacher Institute, 2018). Unintended pregnancy mainly results from not using
contraception or inconsistent or incorrect use of effective contraceptive methods
(Guttmacher Institute, 2018). Women more likely to experience unintended births include
unmarried women, African American women, and women with less education or income
(Guttmacher Institute, 2018).
Epidemiology. In 2011, nearly half (45% or 2.8 million) of the United States'
pregnancies were not intended, with 45 unintended pregnancies per every 1,000 women

aged 15–44 (Finer & Zolna, 2016; Guttmacher Institute, 2018). This equates to nearly 5%
of reproductive age women experiencing an unintended pregnancy each year (Finer &
Zolna, 2016). Race disparities in unintended pregnancy exist, with 69% of African
American women identifying their pregnancies as unintended compared to 42% of
Caucasian women (Barber et al., 2015). At 79 per 1,000, the unintended pregnancy rate
for African American women in 2011 was more than double that of non-Hispanic
Caucasian women (33 per 1,000) (Finer & Zolna, 2016; Kusunoki et al., 2016). This
disparity is similar to the percentage of unintended births (Finer & Zolna, 2016; Kusunoki
et al., 2016). African American women have their first child earlier (age 20.9, verse 24.1)
and have more children (2.4 verse 2.2) than Caucasian women (Kusunoki et al., 2016).
The highest unintended pregnancy rates in 2011 were among women in their late teens
and twenties. The age group rate per thousand was 105 (18–19 years old), 101 (20–24
years old), and 69 (25–29 years old) with an overall increased rate of unplanned
pregnancies in women aged 18–25 (Barber et al., 2015; USDHHS 2019).
Rates of unintended pregnancy are generally highest in the south, southwest, and
densely populated states (Kost, 2015). Approximately 55% of unintended pregnancies in
the United States occur in poor and cohabitating young adult women aged 18–24, who
are much less likely to use contraception than older women, more likely not to seek
prenatal care, and have unmet support needs and emotional and financial difficulties
(Finer & Sonfield, 2013; Gray, 2015; Kornides et al., 2015). Kim et al. (2016) found that
African American women were less likely to use and have correct information about

47
hormonal methods and long-term contraceptive methods than their Caucasian
counterparts.
Implications. In 2011, 42% of unintended pregnancies, excluding miscarriages,
ended in abortion, and 58% ended in birth. This represents a small shift from 2008 when
40% ended in abortion, and 60% ended in birth (Finer & Zolna, 2016). The proportion of
unintended pregnancies ending in birth decreased across all racial and ethnic subgroups
between 2008–2011. The proportion of women experiencing an unintended pregnancy
and choosing to end it in abortion was higher among African American women than
among women in other racial and ethnic groups (Finer & Zolna, 2016). More than half of
all women in the United States will experience an unintended pregnancy by the time they
reach age 45 (Finer & Zolna, 2016).
The estimated cost of unintended pregnancy in the United States as of 2013 was
$4.6 billion annually, with 53%, or $2.5 billion each year, due to inconsistent
contraceptive use (Finer & Sonfield, 2013). By helping women avoid unintended
pregnancies, publicly funded family planning services saved taxpayers $13.6 billion, or
$7.09 for every $1 spent (Frost, Sonfield, Zolna, & Finer, 2014).
Summary
Unintended pregnancy is associated with multiple emotional, social, economic,
and health outcomes, which makes it a substantial public health concern. Unintended
pregnancy may lead to disparities in morbidity and mortality due to delayed prenatal care;
reduced breastfeeding; depression; delivery of infants with low birth weight and birth

defects; as well as reduced average income compared to other women (Carter et al., 2013;
James & Rashid, 2013, USDHHS, 2019). African American women aged 18–24 are at
higher risk for unintended pregnancy due to non-use of contraception, inconsistent or
improper use of contraception, and failure to use dual contraceptive methods (Craig et al.,
2014). These are topics covered during CSHE.
The goal of FSHE is to prepare young adults to be sexually healthy (Santelli et al.,
2017). Misconceptions surrounding long-term contraceptive methods remain a large
factor in use disparities among African American young women. Racial and ethnic
disparities involving contraceptive knowledge exist with an association between less
knowledge and use of LECMs, less knowledge, less self-efficacy, and less knowledge
and increased unintended pregnancy. Reproductive trends in contraceptive use among
African American women may be impacted by a reproductive history of medical and
reproductive abuse. The United States has a history of social and legislative policies to
control poor and minority women's reproductive health through forced sterilization.
FSHE, for most, is received through school based programs, which may not be
comprehensive and often have moral undertones.
African American women are exposed to higher teen and single parenthood rates,
earlier sexual initiation, and use contraception less effectively (Barber et al., 2015).
Perceived social norms involving sexuality, contraceptive selection, and pregnancy
shaped by familial experiences may cause African American women to be more likely to
have inconsistent contraceptive usage and use LECMs. Anecdotal information and

49
personal experiences learned or experienced in the south may supersede formal education
for African American young women. Current research involving contraception among
African American women is limited to either small qualitative studies or large surveys
focusing on nonuse. The focus of this study was to evaluate the impact of FSHE on
sexual initiation, contraceptive use, and contraceptive selection among African American
young women aged 18–24 who have sex with men. An understanding of the impact of
FSHE may lead to the development of interventions designed to prevent unintended
pregnancies through increased consistent, preference, and intention matched
contraceptive use, as well as improved maternal health and reduced adverse birth
outcomes, all of which public health concerns among young African American women.
Provided in Chapter 3 are details of how the NSFG was used to investigate the
extent to which knowledge gained through FSHE impacts sexual initiation and
contraceptive use and selection among African American women aged 18 24 in the
United States who have sex with men. Presented and interpreted in Chapter 4 are the
results of the statistical analysis techniques discussed in Chapter 3. In Chapter 5 the study
findings are compared to existing empirical literature, and implications and proposed
solutions are discussed.
Chapter 3: Research Method
Purpose of the Study
The purpose of this study was to complete a quantitative analysis of the 2015–
2017 NSFG to explore the impact receipt of FSHE has on sexual initiation and

contraception use and selection among African American young women aged 18–24 in
the United States who have sex with men. Information from this study may lead to the
provision of culturally competent services that increase CSHE, raise the age of sexual
initiation, and increase consistent use of preference and intention matched contraceptive
use among sexually active African American women aged 18–24 in the United States
who have sex men. Information from this study may also decrease unintended
pregnancies, impact maternal health, and reduce adverse birth outcomes public health
concerns in young African American women (Kornides et al., 2015).
In this chapter, I provide information on the study design used for this research
and its supporting rationale. The NSFG population, sampling procedures, procedures for
recruitment, participation, data collection, and operationalization of variables are
discussed. The data analysis plan is outlined, and threats to validity and ethical
procedures are described.
Research Design and Rationale
I conducted this study using a quantitative cross-sectional research approach to
investigate NSFG variables related to FSHE and contraception selection, use, and sexual
initiation among African American young women aged 18–24 in the United States who
have sex with men. Participants' receipt of FSHE before 18 years of age was the
independent variable. If participants self-reported receipt of FSHE, I analyzed responses
to determine if education was ACSHE, APSHE, or CSHE based on coverage of birth

51
control methods, where to get birth control, how to use a condom, and waiting until
marriage to have sexual intercourse. Age of sexual initiation and selection of no method,
LECMs, MECMs, and HECMs served as dependent variables.
The NSFG provides the most comprehensive and nationally representative
assessment of reproductive health in the United States. I selected the NSFG as the data set
for this study due to its oversampling of African American women and individuals aged
15–24. As part of the federal statistical system, National Center for Health Statistics
(NCHS) supports disseminating the NSFG public use data and documentation files at no
charge to the public. I obtained secondary data from the NSFG public domain website. I
analyzed data from the NSFG through descriptive statistics, logistic regression, and
multinomial logistic regression. Lindberg and Maddow-Zimet (2012) used a similar
strategy to analyze the impact of sexual education on adult sexual behaviors by using
multinomial logistic regression to examine associations between sexual health education
and sociodemographic covariates, and sexual behaviors. Jaramillo et al. (2017) used
multinomial logistic regression to ascertain associations between exposure to sexual
health education topics and contraception used at last sex. Bourke et al. (2014) explored
the receipt of FSHE and sexual initiation using multinomial logistic regression.
Methodology
Population
The NSFG provides information on family life, marriage and divorce, pregnancy,
infertility, use of contraception, and general and reproductive health on a nationally

representative sample of the civilian, noninstitutionalized United States population aged
15-49 based on voluntary, in-person CAPI. The NSGF continuously interviews the U.S.
population, in 12 week intervals, annually over 48 weeks. The 2015–2017 NSFG includes
5,554 interviews conducted with women aged 15–49 from September 2015 to September
2017 (CDC, 2019b). Of this population, 1,355 were non-Hispanic Black women (CDC,
2019b).
Sampling and Sampling Procedures
The NSFG is a multi-staged probability based, nationally representative sample of
individuals aged 15–49. For this study, I used a cross-sectional approach involving
secondary public use data from the 2015–2017 NSFG for African American women aged
18–24 who have sex with men. The NSFG utilizes a sample design that obtains a sample
size of at least 5,000 interviews per year, and oversamples non-Hispanic Blacks,
Hispanics, and teens aged 15–19 (CDC, 2019b). The goal is that interviewees be 20%
non-Hispanic Black, 20% Hispanic, 55% female, and 20% teens aged 15–19, resulting in
a nationally representative sample (CDC, 2019b).
The NSFG uses a stratified five stage area probability sampling method based on
probability proportionate to size (PPS) selection in four domains to ensure the
oversampling of non-Hispanic Blacks, Hispanics, and teens (CDC, 2019b; see Table 2).
Households in domains 2 through 4 are given higher weights to increase the likelihood of
being selected. The first two participant selection stages used these weighted measures
(CDC, 2019b).

53
Table 2
Probability Proportionate to Size Domain Definition and Characteristics Based on
Household
Domain Definition Total Households Estimated Proportion
Black
Estimated Proportion
Hispanic
1 <10% HH Black
<10% HH Hispanic 65,009,685 .018 .022
2 >=10% HH Black
<10% HH Hispanic 19,871,976 .426 .029
3 <10% HH Black
>= HH Hispanic 20,270,438 .026 .380
4 >=10% HH Black
>=10% HH Hispanic 11,564,194 .301 .299
Note. Reproduced from the 2015-2017 National Survey of Family Growth (NSFG): Sample design documentation by the Centers for
Disease Control and Prevention, 2019b.
Selection of primary sampling units (PSUs).
The NSFG divides the United States into 2,149 PSUs, of which 366 are
considered metropolitan statistical areas (MSAs), and 1,783 are non-MSAs (CDC,
2019b). Each PSU is stratified according to census division, size, and PPS domain. PSUs
with larger populations are assigned a higher selection probability (CDC, 2019b). To
ensure that sampling rates are approximately equal for all households within a sampling
domain, first stage selection probabilities are inversely related to the probabilities of
selection at the second and third stages of selection (CDC, 2019b).
Two-hundred and thirteen PSUs plus two for Alaska and Hawaii are automatically
included in the national probability samples (CDC, 2019b). Of these, 21 PSUs are
considered self-representing (SR) due to population size, and 192 PSUs are considered
non-self-representing (NSR), representing themselves as well as other NSR PSUs (CDC,

2019b). A subset of these 215 PSUs is selected for each 2 year sampling period (CDC,
2019b).
Selection of secondary sampling units (SSUs).
PSUs are segmented into SSUs comprised of one or more census blocks with at
least 50 housing units (HUs) in urban locations and 75 in rural locations (CDC, 2019b).
Most PSUs had 12 SSUs (CDC, 2019b). However, domains 2 through 4 had a higher
selection rate to ensure that African American and Hispanic participants constitute 20%
of all interviews (CDC, 2019b). Segments with fewer than 12 SSUs increased HU size to
60 to 120 based on location (CDC, 2019b).
Listing and selection of HUs within SSUs.
Lists of HUs to be interviewed were generated via the U.S. Postal Service’s
delivery sequence file (DSF) or from a scratch list (CDC, 2019b). The scratch list
consisted of rural and post office box addresses. NSFG personnel physically checked
addresses on the scratch list. Based on these lists, segment maps are developed using
topologically integrated geographical encoding files and geographic information system
(GIS) software. Maps included a view of each segment according to a large scale location
view based on relation to major highways and streets, an intermediate view relative to
major streets and block boundaries, and a detailed small scale view outlining individual
blocks. Maps and DSF addresses are loaded into an electronic listing application and
provided to interviewers one to two months before data collection so that addresses can

55
be verified and updated if needed. Interviewers also are provided with supplemental
information regarding issues that could impact data collection, such as restricted access
areas and potentially dangerous locations.
Selecting one of the eligible persons within each sampled household.
During the screening activity, the NSFG researchers asked an adult member of the
household to list each resident's gender, age, and race or ethnicity. Information was
requested regarding college students, and those residing in dormitories were listed as part
of their parents’ household, while those with apartments were not. If there was not a
resident between the age of 15 to 49 years of age, the interview was terminated. If more
than one eligible resident was found, the CASI system made the section of which
individual to survey based on meeting target sample sizes for teens and females. Within
household selection rates were designed so that 20% of interviews were conducted with
teens aged 15–19, and 55% of all interviews were females (CDC, 2019b, 2019c).
Two-phase sampling for nonresponses.
During the first 10 weeks of phase-one sampling, unscreened addresses received a
sorry I missed you card and were marked for continuous follow up. Addresses that were
still unscreened during phase two of sampling receive a mailed incentive during the last
two weeks of sampling to encourage participation and more intense follow up. The final
public use data is based on a final weighting design developed from poststratification
adjustment factors and weight trimming. Poststratification was limited to age, gender, and
race and ethnicity based on population estimates from the U.S. Census Bureau and CPS

analysis. Weight trimming was used to reduce the estimated variance without increasing
nonresponse bias. Based on the probability of selection, nonresponse rate, and
poststratification factors, weights at the first and 99th percentiles were conservatively
trimmed. Cases not trimmed had their weights increased so that the sum of weights were
equal to the population control.
Procedures for Recruitment, Participation, and Data Collection
The survey population included college students living in dormitories and
fraternity and sorority housing and military personnel living off base. Excluded from the
survey were individuals residing in prisons, homes for juvenile delinquents, homes for the
intellectually disabled, long-term psychiatric hospitals, and military bases. All HUs
selected used the stratified five stage area probability sampling method were mailed an
advance household letter and NSFG question and answer brochures. These documents
provided information on the survey, explained that completion of the survey was
voluntary, informed potential participants that an interviewer would visit their home
within a few days, and offered a $40 token of appreciation for completion. On the day of
data collection, NSFG interviewers visited HUs selected using the stratified five stage
area probability sampling method, which received the mailed documentation. If no one
was home, a sorry I missed you card was left, and a return visit was made during a
different day or time of day. If the potential participant was home, but unable to complete
the survey, the interviewer answered any questions regarding the survey and offered to
return at a more convenient time.

57
Individuals willing to participate in the survey completed a 5 minute screener to
ensure they met age and matched the stratified five stage area probability sampling
method requirements. Individuals who passed the screening were provided a respondent
letter, which explained the selection for the survey and received a copy of the informed
consent form; all documentation was provided in English and Spanish. Participants
provided an electronic signature acknowledging informed consent and received a $40
token of appreciation in advance of completing the interview. Per an NCHS ERB granted
waiver of informed consent documentation, participants were not required to sign the
electronic consent form. For those that elected not to sign, the interviewer signed the
consent form acknowledging that the participant received informed consent information
and that the respondent agreed to participate in the survey. NSFG researchers presented
individuals not selected for participation based on the screening process, a $5 token of
appreciation for completing the screener.
Interviews were conducted over 60–80 minutes and administered either by CAPI
or ACASI. In ACASI, the respondent listens to the questions through headphones, reads
them on the screen, or both, and enters the response directly into the computer. The
NSFG researcher administered the majority of surveys via ACASI, as this method avoids
asking the respondent to provide answers to the interviewer, increasing the complete
reporting of sensitive behaviors.
As part of the federal statistical system, NCHS supports disseminating the NSFG
public use data and documentation files at no charge to the public. The NSFG public use

data for the 2015–2017 survey is housed on its website and includes program statements,
syntax guidelines to read the ASCII data into statistical software, and informed consent
documentation. I obtained secondary data from the NSFG public domain website.
Permission for NSFG data use is not required; however, the citation of data is requested.
Operationalization of Constructs
NSFG 2015–2017 variables related to FSHE, age of sexual initiation, and
contraceptive use and method selected for vaginal intercourse at sexual initiation and
within the 12 months before the survey were analyzed to explore the impact receipt of
FSHE has on sexual initiation and contraception use and selection among African
American young women aged 18–24 who have sex with men. Variables analyzed include
(see Table 3).
Demographics. Participants included in the secondary data analysis were African
American (RSCRRACE) and between the ages of 18–24 (RSCRAGE/AGER).
Ever had sex. Participants included in the secondary data analysis had vaginal
intercourse (RHADSEX/HADSEX).
FSHE received. Participants' receipt of FSHE before 18 years of age (SEDNO)
was categorized as received (yes) or not received (no). If received, responses determined
if education was ACSHE, APSHE, or CSHE based on coverage of methods of birth
control (SEDBC), coverage where to get birth control (SEDWHBC), coverage of how to
use a condom (SEDCOND), and waiting until marriage to have sexual intercourse
(SEDABST). FSHE was ACSHE if education on waiting until marriage (SEDABST) was

59
the only variable answered as yes; APSH, if yes, were the answers to variables SEDBC
and SEDABST; and CSHE, if yes, were the answers to variables SEDBC, SEDWHBC,
SEDCOND, and SEDABST.
Sexual initiation. Participants’ responses to, “The very first time that you had
sexual intercourse with a man, how old were you?” (AGEFSTSX) was categorized as
under 15, 15–17, 18–19, and 20 or over.
Table 3
2015–2017 National Survey of Family Growth Variables Analyzed
NSFG variables Question Responses
RSCRRACE Respondent’s race as reported in the screener
1 Other,
2 Black or
African American
3 White
4 Hispanic
RSCRAGE/AGER Respondent’s age as reported in the screener 18–24
RHADSEX/HADSEX Whether respondent has ever had sex (Vaginal Intercourse) with a
man
1 Yes
2 No
AGEFSTSX The very first time that you had sexual intercourse with a man, how
old were you?”
0–24
SEDNO
Now I’m interested in knowing about formal sex education you
may have had. (Before you were 18, did/have) you ever
(have/had) any formal instruction at school, church, a community
center, or some other place about how to say no to sex?
1 Yes
5 No
SEDABST
Before you were 18, did/have) you ever (have/had) any formal
instruction at school, church, a community center, or some other
place about waiting until marriage to have sex?
1 Yes
5 No
SEDBC
(Before you were 18, did/have) you ever (have/had) any formal
instruction at school, church, a community center, or some other
place about methods of birth control?
1 Yes
5 No
(Before you were 18, did /have) you ever (have/had) any formal 1 Yes
SEDWHBC instruction at school, church, a community center, or some other 5 No
place about where to get birth control?
SEDCOND
(Before you were 18, did/have) you ever (have/had) any formal
instruction at school, church, a community center, or some other
place about how to use a condom?
1 Yes
5 No
Usefstsx Whether R used a method at first sex 1 Yes
5 No
FIRSMETH1 What was the first birth control method you ever used for any
reason?
1 No method
3 Birth control pills
4 Condoms
7 Withdrawal 8
Depo-Provera,
injectables

9 Hormonal implant
(Norplant, Implanon,
or Nexplanon) 10
Calendar rhythm,
standard days, or
cycle beads method
LSTMTHP1 If R used a method at last intercourse with the last partner 12 Diaphragm
in the past 12 months, what method did you or he use? 13 Female condom
14 Foam
15 Jelly or cream
17 Suppository
18 Sponge
19 IUD, coil, or loop
25 Contraceptive patch
26 Vaginal contraceptive ring
Contraceptive selection and use. The NSFG researchers measured contraceptive
use (usefstsx) at sexual initiation. The contraceptive method used at sexual initiation
(FIRSMETH) and last intercourse (FSTMTHP) is outlined in Table 4.
Table 4
2015–2017 National Survey of Family Growth Contraceptive Methods
Value Label
3 Birth Control Pills
4 Condoms
7 Withdrawal
8 Depo-Provera, injectables
9 Hormonal implant (Norplant, Implanon, or Nexplanon)
10 Calendar rhythm, standard days, or cycle beads method
12 Diaphragm
13 Female condom
14 Foam
17 Suppository
18 Sponge
19 IUD, coil, or loop
25 Contraceptive patch
26 Vaginal contraceptive ring
For this study, barrier methods including condoms, diaphragms, sponges, and
spermicides, including foam and suppositories, are classified as LECMs, with hormonal
methods including oral contraceptives, and patch ring, and injectables classified as

61
MECMs. IUDs and hormonal implants are classified as HECMs. Withdrawal and rhythm
methods are classified as not having used contraceptives. Contraceptive methods
categories are outlined in Table 5.
Table 5
Variables Created for Analysis
Created Variables Based on NSFG Variables Required Responses
ACSHE SEDABST 1 Yes
APSHE SEDABST and SEDBC yes response 1 Yes
CSHE SEDABST, SEDBC, SEDCOND, and
SEDWHBC yes responses 1 Yes
AgeFirstSex agefstsx
0 = 0–13
1 = 14–17
2 = 18–19
3 = 20–24h
Contraceptive
Methods used at
first and last sex
0. No contraceptive used
1 No method
7 Withdrawal
10 Calendar rhythm, standard days, or cycle beads method
1. Less effective method
4 Condoms
12 Diaphragms
14 Foam
15 Jelly or cream
17 Suppository
18 Sponge
2 Moderately effective method
3 Birth control pills
8 Depo-Provera, injectables
3 Birth control pills
8 Depo-Provera, injectables
25 Contraceptive patch
26 Vaginal contraceptive ring
9 Hormonal implant (Norplant, Implanon, or Nexplanon)
3. Highly effective method
19 IUDs, coil or loop
Data Analysis Software, Data Cleaning and Preparation for Public-Use
I used the IBM Statistical Package for the Social Sciences (SPSS 25)
statistical software to complete the data analysis described in this section. NSFG data are
prepared for public use via hard edits, which prevented values that were inconsistent with

answers to related variables, and soft edits, which noted answers that were rare or
improbable (CDC, 2019a, 2019c). Participants were able to correct these responses. If a
participant elected to skip a question, the interview coded the response as not ascertained
with values of 7, 97, 997, 9997, or 99997 (CDC, 2019a, 2019c). If a participant refused to
answer a question, the interviewer coded the response as refusal with values of 8, 98, 998,
9998, or 99998 (CDC, 2019a, 2019c). The NSFG researchers checked the consistency of
responses with recoded variables. Missing or inconsistent variables received new codes
using sequential regression imputation to predict a value for the missing or inconsistent
data or via logical imputation by an NCHS subject matter expert who examined related
variables and assigned a consistent value (CDC, 2019a, 2019c).
The percentage of recoded imputed values did not exceed 2% for any variable
(CDC/NCHS, 2019a, 2019c).
Research Questions and Data Analysis Plan
The RQs for this study are as follows:
RQ1: Is there an association between the type of FSHE received and the age of
sexual initiation among sexually active African American women aged 18–24 who have
sex with men?
H01: There is no association between the type of FSHE received and the age of
sexual initiation among sexually active African American women aged 18–24 who have
sex with men.

63
H11: There is an association between the type of FSHE received and the age of
sexual initiation among sexually active African American women aged 18–24 who have
sex with men.
To answer RQ1, I used multinomial logistic regression to determine the
association between the self-reported type of FSHE received (abstinence-centered,
abstinence-plus, or comprehensive) and the age category of sexual initiation (0–13, 14–
17, 18–19, and 20 and over) for sexually active African American women aged 18–24
who have sex with men. ACSHE and the 0–13 age category were the referent groups. I
used odds ratios (OR) to measure the strength of the association. OR confidence intervals
(CI) were set at 95%, and the critical p-value significance was .05.
RQ2: Is there an association between the type of FSHE received and contraceptive
use at sexual initiation for sexually active African American women aged
18–24? who have sex with men
H02: There is no association between the type of FSHE received and contraceptive
use at sexual initiation among sexually active African American women aged 18–24 who
have sex with men.
H12: There is an association between the type of FSHE received and contraceptive
use at sexual initiation among African American women aged 18–24 who have sex with
men.
To answer RQ2, I used logistic regression to determine the association between
the self-reported type of FSHE received (abstinence-centered, abstinence-plus, or

comprehensive) and contraceptive use (yes/no) at sexual initiation for African American
women aged 18–24 who have sex with men. ACSHE and no contraceptive use were the
referent groups. ORs were used to measure the strength of the association. OR CIs were
set at 95%, and the critical p-value significance was .05.
RQ3: Is there an association between the type of FSHE received and the
effectiveness of contraceptive methods selected at sexual initiation by sexually active
African American women aged 18–24 who have sex with men?
H03: There is no association between the type of FSHE received and the
effectiveness of contraceptive methods selected at sexual initiation by sexually active
African American women aged 18–24 who have sex with men.
H13: There is an association between the type of FSHE received and the
effectiveness of the contraceptive method selected at sexual initiation by sexually active
African American women aged 18–24 who have sex with men.
To answer RQ3, I used multinomial logistic regression to determine the
association between the type of self-reported FSHE received (abstinence-centered,
abstinence-plus, or comprehensive) and effectiveness of contraceptive method selected
(none, less effective, moderately effective, and highly effective) at sexual initiation by
sexually active African American women aged 18–24 who have sex with men. ACSHE
and no contraceptive method selected were the referent groups. ORs were used to
measure the strength of the association. OR CIs were set at 95%, and the critical p-value
significance was .05.

65
RQ4: Is there an association between the type of FSHE received and the
effectiveness of contraceptive methods primarily selected by sexually active African
American women aged 18–24 who have sex with men at last intercourse within the past
12 months?
H04: There is no association between the type of FSHE received and the
effectiveness of the contraceptive method primarily selected by sexually active African
American women aged 18–24 who have sex with men at last intercourse within the past
12 months.
H14: There is an association between the type of FSHE received and the
effectiveness of contraceptive methods primarily selected by sexually active African
American women aged 18–24 who have sex with men at last intercourse within the past
12 months.
To answer RQ4, I used multinomial logistic regression to determine the
association between the self-reported type of FSHE received (abstinence-centered,
abstinence-plus, or comprehensive) and effectiveness categories of the contraceptive
method primarily selected (none, less effective, moderately effective, and highly
effective) by sexually active African American women aged 18–24 who have sex with
men at last intercourse within the past 12 months. ORs were used to measure the strength
of the association. OR CIs were set at 95%, and the critical p-value significance was .05.
Threats to Validity
The NSFG sampling procedures addressed external threats to validity. The
researchers selected non-Hispanic African American women and teens aged 15–19 at

higher rates to yield an oversample of the population and weighted the samples to
increase consistency in predictions. NSFG researchers used two-phase sampling methods
to reduce nonresponse bias. Recall bias may have occurred due to the inability to recall
first sexual experiences or the type of sex education they received. Under-reporting and a
social desirability bias may have occurred due to respondents giving what they viewed as
socially desirable instead of truthful answers. The administration of the majority of
surveys was via ACASI to increase the complete reporting of sensitive behaviors. There
were no perceived internal threats to conducting this study, as it was a secondary data
analysis.
Ethical Procedures
Internal Procedures
The process for Walden University's Institutional Review Board (IRB) approval
consisted of the submission of the proposal draft to the assigned University Research
Reviewer (URR). I submitted the description of data sources and partner sites to request
guidance from an IRB staff member on completing the IRB process. I completed and
revised applicable student forms, and approval documentation based on guidance
received according to the preliminary ethics feedback service. After proposal approval, I
completed applicable student forms and approval documentation and revised them as
needed to submit for final IRB approval. The IRB number assigned to this research is 01-
27-20-0107579.

67
External Procedures
An individual who passed the screening process received a respondent letter,
which explained selection for the survey, along with a copy of the informed consent
form; both were available in English and Spanish. These documents emphasized
confidentiality and provided participants with the NSHS research ethics review board’s
toll-free number and the study number. Also provided was a dedicated website to answer
any questions about the study. Participants provided an electronic signature
acknowledging informed consent. Per an NCHS ERB granted waiver of informed consent
documentation, participants were not required to sign the electronic consent form. For
those that elected not to sign, the interviewer signed the consent form acknowledging the
provision of informed consent information and that the respondent agreed to participate in
the survey.
Proposed NSFG public use files were reviewed by NCHS Disclosure Review
Board (DRB) before release, where several variables were suppressed or modified to
prevent the disclosure of participants' identity. Several suppressed and modified variables
are available for a fee from the NCHS Research Data Center (RDC). Directly identifying
information, including names and addresses, are suppressed from public use files. The
REGION of residence variable is suppressed but is available from the RDC for a fee. Life
events such as marriages, divorces, pregnancies, cohabitations, educational degrees,
military service, and selected health services are suppressed to prevent potential linkages
or use with external data sources to identify respondents (CDC, 2019b, 2019c). The

variable for the Hispanic subgroup (HISPGRP) has been modified and collapsed for
public use, with full detail available from the RDC for a fee. The values of some variables
were randomly altered through statistical perturbation to prevent the identification of
respondents.
The NSFG houses public use archival data on its website from 1973–2017. As
part of the federal statistical system, NCHS supports disseminating the NSFG public use
data and documentation files. Since the inception of the study, variables are suppressed or
modified on the public use data files to protect the survey respondents' identity and
confidentiality. The REGION variable was not suppressed in surveys conducted before
2015–2017.
Summary
In this chapter, I discussed the methodology and research plan for a quantitative
cross-sectional analysis of the 2015–2017 NSFG designed to investigate the extent to
which knowledge gained through FSHE impacts sexual initiation and contraceptive use
and selection sexually active African American women aged 18–24 in the United States
who have sex with men. Descriptive statistics were used to define demographics,
providing the number of self-reported sexually active African American women aged 18–
24. I used multinomial logistic regression to determine the association between the
selfreported type of FSHE received and self-reported age of sexual initiation among
sexually active African American women aged 18–24 who have sex with men. I used
binary logistic regression to determine the association between the self-reported type of
FSHE received and self-reported contraceptive use at sexual initiation for African

69
American women aged 18–24 who have sex with men. I used multinomial logistic
regression to determine the association between the type of self-reported FSHE received,
self-reported age of sexual initiation, and effectiveness of self-reported contraceptive
method selected at sexual initiation by sexually active African American women aged
18–24. I used multinomial logistic regression to determine the association between the
self-reported type of FSHE received and effectiveness of self-reported contraceptive
methods selected by sexually active African American Women selected at last intercourse
within the past 12 months. OR CI was 95%, and the critical p-value significance was .05.
Racial and ethnic disparities involving contraceptive knowledge exist with an
association between less knowledge and use of LECMs, less self-efficacy, and increased
unintended pregnancy (Kim et al., 2016). Disparities also exist involving African
American young women experiencing earlier sexual initiation. Key results from this
study may lead to an increase in the provision of culturally competent services, such as
sexuality and reproductive education, family planning, and contraceptive counseling. This
may increase African American young women’s selection and consistent use of
contraceptive methods best fit for reproductive intentions, reduce usage failures, decrease
the age of sexual initiation, and improve birth related outcomes. Key results from this
study may also decrease unintended pregnancies and reduce adverse birth outcomes.
Presented and interpreted in Chapter 4 are the results of the statistical analysis
techniques discussed in this chapter. The study findings are compared to existing
empirical literature, and implications and proposed solutions are discussed in Chapter 5.

Chapter 4: Results
Introduction
The nature of this quantitative cross-sectional analysis of the 2015–2017 NSFG
was to explore the receipt of FSHE and the impact it may have on sexual initiation,
contraceptive use and selection among African American women aged 18–24 who have
sex with men. The results of this study may highlight the importance and increase
provisions of FSHE, which may raise the age of sexual initiation, lead to consistent use of
preference and intention matched contraceptives, and reduce contraceptive failures due to
improper use.
In this chapter, I explore the following RQs:
RQ1: Is there an association between the type of FSHE received and the age of
sexual initiation among sexually active African American women aged 18–24 who have
sex with men?
H01: There is no association between the type of FSHE received and the age of
sexual initiation among sexually active African American women aged 18–24 who have
sex with men.
H11: There is an association between the type of FSHE received and the age of
sexual initiation among sexually active African American women aged 18–24 who have
sex with men.
RQ2: Is there an association between the type of FSHE received and contraceptive
use at sexual initiation for sexually active African American women aged

71
18–24 who have sex with men?
H02: There is no association between the type of FSHE received and contraceptive
use at sexual initiation among sexually active African American women aged 18–24 who
have sex with men.
H12: There is an association between the type of FSHE received and contraceptive
use at sexual initiation among African American women aged 18–24 who have sex with
men.
RQ3: Is there an association between the type of FSHE received and the
effectiveness of contraceptive methods selected at sexual initiation by sexually active
African American women aged 18–24 who have sex with men?
H03: There is no association between the type of FSHE received and the
effectiveness of contraceptive methods selected at sexual initiation by sexually active
African American women aged 18–24 who have sex with men.
H13: There is an association between the type of FSHE received and the effectiveness
of the contraceptive method selected at sexual initiation by sexually active
African American women aged 18–24 who have sex with men.
RQ4: Is there an association between the type of FSHE received and the
effectiveness of contraceptive methods primarily selected by sexually active African
American women aged 18–24 who have sex with men at last intercourse within the past
12 months?

H04: There is no association between the type of FSHE received and the
effectiveness of the contraceptive method primarily selected by sexually active African
American women aged 18–24 who have sex with men at last intercourse within the past
12 months.
H14: There is an association between the type of FSHE received and the
effectiveness of contraceptive methods primarily selected by sexually active African
American women aged 18–24 who have sex with men at last intercourse within the past
12 months.
To answer RQ1, I used multinomial logistic regression to determine the
association between the self-reported type of FSHE received (abstinence-centered,
abstinence-plus, or comprehensive) and age of sexual initiation (0–13, 14–17, 18–19, and
20 and over) for sexually active African American women aged 18–24. ACSHE and the
0–13 age category were the referent groups. ORs were used to measure the strength of the
association. OR CIs were set at 95%, and the critical p-value significance was .05.
To answer RQ2, I used logistic regression to determine the association between
the self-reported type of FSHE received (abstinence-centered, abstinence-plus, or
comprehensive) and contraceptive use (yes/no) at sexual initiation for African American
women aged 18–24. ACSHE and no contraceptive use were the referent groups. ORs
were used to measure the strength of the association. OR CIs were set at 95%, and the
critical p-value significance was .05.

73
To answer RQ3, I used multinomial logistic regression to determine the
association between the type of self-reported FSHE received (abstinence-centered,
abstinence-plus, or comprehensive) and effectiveness of contraceptive method selected
(none, less effective, moderately effective, and highly effective) at sexual initiation
according to sexually active African American women aged 18–24. ACSHE and no
contraceptive method selected were the referent groups. ORs were used to measure the
strength of the association. OR CIs were set at 95%, and the critical p-value significance
was .05.
To answer RQ4, I used multinomial logistic regression to determine the
association between the self-reported type of FSHE received (abstinence-centered,
abstinence-plus, or comprehensive) and effectiveness of contraceptive methods primarily
selected (none, less effective, moderately effective, and highly effective) according to
sexually active African American women aged 18–24 at last intercourse within the past
12 months. ORs were used to measure the strength of the association. OR CIs were set at
95%, and the critical p-value significance was .05.
In this chapter, I provide information on NSFG data collection and descriptive and
demographic characteristics and statistics of the sample population. I also present,
interpret, and summarize results for the statistical analysis techniques above with
applicable tables and statistics.

Data Collection
The NSGF continuously interviews the U.S. population, in 12 week intervals,
annually over 48 weeks. The 2015–2017 NSFG includes 5,554 interviews conducted with
women aged 15–49 from September 2015 to September 2017. Of this population, 1,355
were non-Hispanic Black women. The NSFG uses a multi staged probability based
nationally representative sample design that minimizes the design effects of women and
men, obtains a sample size of at least 5,000 interviews per year, and oversamples
nonHispanic Blacks, Hispanics, and teens aged 15–19. The goal is that interviewees are
20% non-Hispanic Black, 20% Hispanic, 55% female, and 20% teens aged 15–19,
resulting in a nationally representative sample (CDC, 2019b).
The final public use data are based on a final weighted design developed from
poststratification adjustment factors and weight trimming. Poststratification is limited to
age, gender, and race and ethnicity-based on population estimates from the U.S. Census
Bureau and CPS analysis. As such, when weighted to reflect the U.S. female population
at the interviewing midpoint, generalizations may be made. For this research, I used the
final public use data retrieved online.
Data Cleaning
NSFG data are prepared for public use via hard edits, which prevents inconsistent
values with answers to related variables and soft edits, which noted rare or improbable
answers. Participants were able to correct these responses. If a participant elected to skip
a question, the interview coded responses as not ascertained with values of 7, 97, 997,

75
9997, or 99997 (CDC, 2019a, 2019c). If a participant refused to answer a question, the
interview coded the response as refusal with values of 8, 98, 998, 9998, or 99998 (CDC,
2019a, 2019c). The team checked the consistency of responses with recoded variables.
An NCHS subject-matter expert recoded missing or inconsistent variables were using
sequential regression imputation to predict a value for the missing or inconsistent data or
via logical imputation who examined related variables and assigned a consistent value.
The percentage of recoded imputed values did not exceed 2% for any variable (CDC,
2019a, 2019c).
For this study, a subsample contained 499 sexually active African American
women aged 18–29 who have sex with men. I cleaned this subsample for missing data
and responses such as don’t know and refused, for variables used in this study.
Demographic analysis showed that the response rate for women aged 25–29 was 2%. As
such, this population did not meet 5% and was not a part of the data analysis. Current
research surrounding sexual health education and contraceptive use among young women
focused on those aged 18–24, which aligned this study with current research.
Data cleaning yielded a final sample size of 242 sexually active African American
women aged 18–24 who have sex with men. Responses from this subpopulation
demonstrated that women who experienced sexual initiation over the age of 20 (3.1%)
were less than 5%, so I removed this population from the data analysis.
Data Analysis Procedure and Statistical Assumptions
I used IBM SPSS 25statistical software to complete the data analysis described in
this section. I used multinomial logistic regression for RQ1. Principle assumptions for

multinomial logistic regression are: (a) The dependent variables should be measured at
the nominal level. Age of sexual initiation, the dependent variable, was derived from
continuous data and collapsed into categorical, nominal data, (b) The independent
variables are nominal, with continuous variables coded as categorical. All independent
variables are nominal or categorical, (c) All variables have independence of observations,
and the dependent variables have mutually exclusive and exhaustive categories. All
variables used in this study met these criteria, (d) There should be no multicollinearity.
Bivariate analysis and the chi-square test tested multicollinearity among the nominal
independent variables, (e) There needs to be a linear relationship between any continuous
independent variables and the logit transformation of the dependent variable. I did not use
any continuous independent variables in the analysis of RQ1, and (f) There should be no
outliers, high leverage values, or highly influential points. I did not use any continuous
independent variables in the analysis of RQ1, so these criteria do not apply.
I used binary logistic regression for research RQ2 through 4. Principle
assumptions for binary logistic regression are: (a) The dependent variable is measured on
a dichotomous scale. For RQ 2 through 4, contraception use at sexual initiation and
effectiveness categories of contraceptive methods are dichotomous, (b) There are one or
more independent variables, which can be either continuous or categorical. For RQ 2
through 4, the independent variables are categorical; (c) There should be independence of
observations, and the dependent variable should have mutually exclusive and exhaustive
categories. For RQ 2 through 4, contraception use at sexual initiation and effectiveness

77
categories of contraceptive methods are based on mutually exclusive and exhaustive
categories; and (d) there needs to be a linear relationship between any continuous
independent variables and the logit transformation of the dependent variable. For RQ2
through 4, I did not use any continuous independent variables used.
Results
Demographic Characteristics
Univariate analysis. The final population analyzed included 242 sexually active
African American women aged 18–24 who have sex with men. According to Table 6, the
majority were between 20–24 years of age (77.7%), received CSHE (63.2%), and had at
least a high school diploma or general education diploma (GED) (36.8%). When
surveyed (86.8%), the majority had insurance coverage and viewed religion as important
(57.9%). Most were born to single mothers (61.6%) who had at least a high school
diploma or GED (36.8%) and were 20–24 years old at their birth (29.7%). It is important
to note that most participants were born to mothers less than 24 years old (78.5%). Sexual
initiation began between 14–17 years old (70.2%) for most young women who used
contraception at initiation (67.5%). Most used LECMs during sexual initiation (50.6%).
However, most did not use any method at the last sexual encounter (41.3%) despite
stating they would be very upset if they experienced an unintended pregnancy (30.2%).
Table 6
Univariate Analysis of Characteristics of Included Study Participants
Characteristics of participants N = 242 Percentage (%)
Current age (years) 18–
19
54
22.3

20–24 188 77.7
Formal sexual health education received Abstinence-centered
31
12.8
Abstinence-plus 58 24.0
Comprehensive 153 63.2
Education
Less than high school diploma
23
9.5
High school diploma/GED 89 36.8
2 years of college/associate degree 80 33.1
Bachelor’s degree 38 15.7
Graduate degree 12 5.0
Insurance coverage
No
32
13.2
Yes 210 86.8
Importance of religion
Not important
45
18.6
Very important 140 57.9
Somewhat important 57 23.6
Married parents at participant’s birth
No
149
61.6
Yes 93 38.4
Maternal education
Less than high school diploma
39
16.1
High school diploma/GED 89 36.8
2 years of college/associate degree 77 31.8
Bachelor’s degree 37 15.3
(table continues)
Maternal age at first birth
Age of sexual initiation (years) 0–13
22
9.1
14–17 170 70.2
18–19 50 20.7
Used contraception at sexual initiation
No
78
32.5
Yes 132 67.5
Type of contraception used at sexual initiation
None
6
2.5
Less effective methods 121 50.6
Moderately effective methods 104 43.5
Highly effective methods 8 3.4
< 18 63 27.2
18–19 50 21.6
20–24 69 29.7
25–29 38 16.4
≥ 30 12 5.2

79
Type of contraception used at last sexual encounter None
100
41.3
Less effective methods 62 25.6
Moderately effective methods 58 24
Reaction to an unintended pregnancy
Would not care
28
11.8
Very upset 73 3.2
A little upset 72 29.8
A little pleased 41 16.9
Very pleased 28 11.8
Bivariate analysis. A bivariate analysis was used to determine whether a
significant association existed between the independent and dependent variables and to
provide additional characteristics of included study participants. The bivariate analysis in
Table 7 demonstrates that FSHE (X2 = 1.14, p =.83), mother’s age at first birth (X2 = 3.84,
p =.65), mother’s education (X2 = 8.96, p =.25), participants’ parental marital status (X2 =
1.82, p =.4), and importance of religion (X2 = 5.69, p = .2) all had a positive association
with age of initiation, but the associations were not significant. The only significant,
positive association was between age of sexual initiation and reaction to unintended
pregnancy (X2 = 21.08, p =.01). The bivariate analysis in Table 8 demonstrates that FSHE
(X2 = 2.71, p =.26), mother’s age at first birth (X2 = 2.33, p = .51), mother’s education (X2
= 7, p = .07), participants’ parental marital status (X2 = 1.14, p = .29), importance of
religion (X2 = 1.36, p = .51), and reaction to unintended pregnancy (X2 = .30, p = .99), all

had a positive association with contraceptive use at initiation, but the associations were
not significant.
The bivariate analysis in Table 9 demonstrates that FSHE (X2 = 1.56, p = .46),
mother’s age at first birth (X2 = 3.51, p = .32), mother’s education (X2 = 5.74, p = .13),
participants’ parental marital status (X2 = 0.41, p = .52), importance of religion (X2 = 1.78,
p = .41), and reaction to unintended pregnancy (X2 = 3.80, p = .43), all had a positive
association with contraceptive effectiveness category selected at initiation, but the
associations were not significant. The bivariate analysis in Table 10 demonstrates that
FSHE (X2 = 4.45, p = .64), mother’s age at first birth (X2 = 10.07, p =.33), mother’s
education (X2 = 6.04, p =.74), participants’ parental marital status (X2 = 4.08, p = .29), and
importance of religion (X2 = 3.47, p = .72) all had a positive association with
contraceptive effectiveness category selected at last sex, but the associations were not
significant. The only significant, positive association was between contraceptive
effectiveness category selected at last sex and reaction to unintended pregnancy (X2 =
36.40, p < .01).
Table 7
Bivariate Analysis of Age of Sexual Initiation and Independent Variables
Age of sexual
initiation
0–13 14–17 18–19
Study independent variables n % n % n % n % X2 p
Age of sexual initiation
0–13
22
9.1
-
-
-
-
-
-
-
-
14–17 17
9
70.3 - - - - - - - -
18–19 50 20.7 - - - - - - - -

81
Formal sexual health education received
Abstinence-centered
31
12.8
4
18.2
20
11.8
7
14.
0
Abstinence-plus 58 24.0 6 27.3 40 23.5
12 24.0 1.14 .8
3
Comprehensive 15
3
63.2 12 54.6 11
0
64.7
31 62.0
<18 63 27.2 7 33.3 45 28.0 11 22.0
18–19
20–24
50
69
21.6
29.7
6
3
28.6
14.3
33
48
20.5
29.8
11
18
22.0
36.0 3.84
≥25 50 21.6 5 23.8 35
Mother’s education
Less than high school diploma 39 16.1 8 36.4 23 13.5 8 16.0
High school diploma/GED
2 years of college/associate degree
89
77
36.8
31.8
6
7
27.3
32.8
65
55
38.2
32.4
18
15
36.0
30.0 8.96
Bachelor’s degree or higher 37 15.3 1 4.6 27 25.9 9 18.0
Mother’s age at first birth
Married parents at participants’ birth
No
Yes
Importance of religion
Not important
14
9
93
45
61.6
38.4
18.6
16
6
5
72.7
27.3
22.7
105
65
35
61.8
38.2
20.6
28
22
5
56.0
44.0 1.82
.4
0
10.
0
Very important 14
0
57.9 11 50.0 93 54.7 36 72.0 5.69 .2
0
Somewhat important 57 23.6 6 27.3 42 24.7 9 18.0
Reaction to an unintended pregnancy
Would not care
28
11.6
6
27.3
1
7
10.0
5
10.
0
21.7 10

Very upset
A little upset
73
72
30.2 29.8
3
8
13.6 36.4
61
42
35.9 24.7
9
22
18.0
44.0
21.0
8
.0
1
A little pleased 41 16.9 3 13.6 33 19.4 5 10.0
Very pleased 28 11.6 2 9.1 17 10.0 9 18.0
Table 8
Bivariate Analysis of Contraceptive Use at Sexual Initiation and Independent Variables
Contraceptive use at sexual initiation
No Yes
Study independent variables n % n % n % X2 p
Contraceptive use at sexual initiation
No
78
32.5
-
-
-
-
-
-
Yes 162 67.5 - - - - - -
Formal sexual health education
Abstinence-centered
31
12.8 12
15.4
18
11.1
Abstinence-plus 58 24.0 22 28.2 35 21.6 2.71 .26
Comprehensive 153 63.2 44 56.4 109 67.3
Mother’s education
Less than high school diploma
39
16.1
18
23.1
2
0
1
2.
3
High school diploma/GED
2 years of college/associate degree
89
77
36.8
31.8
21
26
26.9
33.3
67
51
41.4
31.5 7.00 .07
Bachelor’s degree or higher 37 15.3 13 16.7 24 14.8
Married parents at participants’ birth
No
Yes
149
93
61.6
38.4
44
34
56.4
43.6
103
59
63.6
36.4
1.
14
.
29
Importance of religion
Not important
45
18.6
11
14.1
3
2
1
9.

83
7
Very important 140 57.9 49 62.8 91 56.2 1.36 .51
Somewhat important 57 23.6 18 23.1 39 24.1
Reaction to an unintended pregnancy
Would not care
28
11.6
10
12.8
1
8
1
1.
1
Very upset
A little upset
73
72
30.2
29.8
23
22
29.5
28.2
50
49
30.9
30.2 0.30 .99
A little pleased 41 16.9 14 18.0 27 16.7
Very pleased 28 11.6 9 11.5 18 11.1
Table 9
Bivariate Analysis of Contraceptive Effectiveness at Sexual Initiation and Independent
Variables
Contraceptive effectiveness category at sexual
initiation
None–less effective Moderately–highly
effective
Study independent variables n % n % n % X2 p
Contraceptive effectiveness category at
sexual initiation
None–Less Effective 127
53.1
-
-
- -
- -
Moderately–Highly Effective 112 46.9 - - - - - -
Formal sexual health education
Abstinence-centered 31
12.8 14
11.0
16
14.
3
Abstinence-plus 58 24.0 34 26.8 23 20.5 1.56 .46
Comprehensive 153 63.2 79 62.2 73 65.2
Less than high school diploma
39
16.1
1
4
11.0
2
4
21.
4
High school diploma/GED 89 36.8 5 40.2 36 32.1 5.74 .13

1
2 years of college/associate degree 77 31.8 4
0
31.5 37 33.1
Bachelor’s degree or higher 37 15.3 2
2
17.3 15 13.4
Married parents at participants’ birth
No
Yes 14
9
93
61.6
38.4
8
0
4
7
63.0
37.0
66
46
58.9
41.1
0.4
1
.5
2
Importance of religion
Not important
45
18.6
2
4
18.9
1
9
17.
0
Very important 14
0
57.8 6
9
54.3 70 62.5 1.78 .41
Somewhat important 57 23.5 3
4
26.8 23 20.5
Reaction to an unintended pregnancy
Would not care 28
11.6
1
4
11.0
1
4
12.
4
Very upset
A little upset
73
72
30.2 29.8
4
2
3
9
33.1
30.7
30
32
26.8
28.6
3.80 .43
A little pleased 41 17.0 2
2
17.3 19 17.0
Very pleased 28 11.6 1
0
7.9 17 15.2
Table 10
Bivariate Analysis of Contraceptive Effectiveness at Last Sex and Independent Variables
Contraceptive effectiveness category at last sex
None
Less
effective
Moderately
effective
Highly
effective
Study independent variables n % n % n % n % n % X2 p
Contraceptive effectiveness
category at last sex
None 10041.3
-
-
-
-
-
-
-
- - -
Less effective 62 25.6 - - - - - - - - - -
Moderately effective 58 24.0 - - - - - - - - - -
Highly effective 22 9.1 - - - - - - - - - -
Formal sexual health education
Abstinence-centered
31
12.
8
1
2
12.
0
6
9.7
11
19.
0
2
9.
1
Abstinence-plus 58 24.0 22 22.
0
18 29.0 14 24.1 4 18.2 4.45 .64

85
Comprehensive 15363.2 66 66.
0
38 61.3 33 56.9 1
6
72.7
Mother’s age at first birth
20-24 69 29.8 23 33.3 27.5 19
≥25 50 21.5 20 40.0 20.0 17
Mother’s education
Less than high school diploma
39
16.1
1
4
14.0
10
16.1
10
17.3
5
22.7
High school diploma/GED 89 36.8 43 43.0 17 27.4 21 36.2 8 36.4 6.04 .74
2 years of college/associate degree 77 31.8 30 30.0 22 35.5 18 31.0 7 31.8
Bachelor’s degree or higher 37 15.3 13 13.0 13 21.0 9 15.5 2 9.1
Married parents at participants’ birth
No
Yes 149
93
61.6
38.4
69
31
69.0
31.0
35
27
56.4
43.6
32
26
55.2
44.8
13
9
59.1
40.9
4.08
.
25
Importance of religion
Not important
45
18.6
1
8
18.0
12
19.3
13
22.4
2
9.1
Very important 140 57.9 61 61.0 35 56.5 29 40.0 15 68.2 3.47 .72
Somewhat important 57 23.5 21 21.0 15 24.2 16 27.6 5 22.7
Reaction to an unintended pregnancy
Would not care
28
11.5
2
0
20.0
3
4.8
1
1.7
4
18.2
Very upset
A little upset
73
72
30.2
29.8
22
21
22.0
21.0
19
22
30.7
35.5
21
24
36.2
41.4
11
5
50.0
22.7 36.40 <.001
A little pleased 41 17.0 29 19.0 11 17.7 10 17.2 1 4.6
Very pleased 28 11.5 18 18.0 7 11.3 2 3.5 1 4.5
Note.p* < .05
Research Question 1
For RQ1, I explored the association between the type of FSHE received and the
age of sexual initiation among sexually active African American women aged 18–24. To
answer RQ1, I used multinomial logistic regression to determine the association between
the self-reported type of FSHE received (abstinence-centered, abstinence-plus, or

comprehensive) and the age categories of sexual initiation classified as 0–13, 14–17, 18–
19, and 20 years and older for sexually active African American Women aged 18–24. I
did not include the initiation group over 20 years of age and young women 25–29 years
old in the analysis as the percentages of both categories were less than 5%. ACSHE and
the 0–13 age of sexual initiation categories were the referent groups. I used the mother’s
age at first birth, mother’s education, if the participant’s parents were married at their
birth, participant’s religious views, and their reaction to an unintended pregnancy as
covariates. ORs were used to measure the strength of the association with the CIs set at
95%, and the critical p-value significance was .05.
Most young women experienced sexual initiation between 14–17 years old
(70.3%, see Table 6) compared to the ≤13 years old age referent group (9.1%). According
to Table 11, compared to the age of initiation referent group, the odds of experiencing
sexual initiation in the 14–17 years old initiation category was 34% higher (OR = 1.34, p
= .73, 95% CI [0.26, 7.04]) if young women received APSHE and 22% (OR = 1.22 p =
.61, 95% CI [0.57, 2.58] higher if they received CSHE, compared to those who received
ACSHE. The odds of young women in this age of initiation category were 45% (OR =
1.45, p = .64, 95% CI [0.64, 3.29]) higher to be born to mothers between 20–24 years of
age who had an 8.78 (p = .01, 95% CI [1.96, 39.33]) higher likelihood to have a high
school diploma or GED. The odds of their parents being married was 4% (OR =1.04, p
= .95, 95% CI [0.29, 3.73] higher. The likelihood of young women in this age group to
view religion as very important was 81% (OR = 1.81, p = .42, 95% CI [0.43, 7.71])

87
higher than the referent groups. They felt very upset if they experienced an unintended
pregnancy was 11.05 (p = .01, 95% CI [2.05, 59.62]) times higher than the referent
groups.
Of the young women served, 20.7% experienced sexual initiation between the
ages of 18–19 (see Table 6). According to Table 11, compared to the age of initiation
referent group, the odds of experiencing sexual initiation in the 18–19 years old initiation
category was 5% (OR = 1.05, p = .98, 95% CI [0.16, 7.01]) higher if young women
received APSHE and 5% (OR = .95, p = .98, 95% CI [0.41, 2.23]) lower if they received
CSHE, compared to those who received ACSHE. Compared to the referent group (0–13
years of age), the odds of the young women in this age of initiation group were 2.25 (p =
.8, 95% CI [0.91, 5.59]) higher to be born to mothers between 20–24 years old who had a
7.34 (p = .02, 95% CI [1.30, 41.36]) higher likelihood to have a high school diploma or
GED. The odds of their parent being married were 40% (OR = 1.40, p = .63, 95% CI
[0.35, 3.63]) higher. The likelihood of young women in this age group to view religion as
very important was 5.07 (p = .06, 95% CI [0.92, 28.07]) higher and to feel very upset if
they experienced an unintended pregnancy was 4.10 (p = .16, 95% CI [0.56, 31.03]) times
higher than the referent groups.
Although the odds of being in an older category for the age of sexual initiation
among sexually active African American women aged 18–24 increased with APSHE and
CSHE compared to the referent group (0–13 years of age), the odds were not significant.

The age of initiation was still within a normative age range. As such, I failed to reject the
null hypothesis.

Research Question 2
For RQ1, I explored the association between the type of FSHE received and
contraceptive use at sexual initiation for sexually active African American women aged
18–24. To answer RQ2, I used logistic regression to determine the association between
the self-reported type of FSHE received (abstinence-centered, abstinence-plus, or
comprehensive) and contraceptive use (yes/no) at sexual initiation for African American
women aged 18–24. Young women 25–29 years of age were not included in the analysis
due to being omitted in the previous research question due to the group's percentage being
less than 5%. I used ACSHE and no contraceptive use at sexual initiation as the referent
groups. ORs were used to measure the strength of the association with the CIs set at 95%,
and the critical p-value significance was .05.
At sexual initiation, 67.5% of young women self-reported contraceptive use (see
Table 6). According to Table 12, the odds of contraceptive use at sexual initiation
increased by 14% (OR = 1.14, p = .80, 95% CI [0.42, 3.09]) with receipt of APSHE and
38% (OR = 1.38, p = .17, 95% CI [0.87, 2.19]), compared to those who received ACSHE.
Young women who used contraception at sexual initiation were 45% (OR = 0.55, p
= .19, 95% CI [0.23, 1.35]) less likely to be born to mothers 18–19 years old, the
likelihood that they were born to mothers with at least a high school diploma or GED was
2.91 (p =
.02, 95% CI [1.21, 7.01]) higher. Their parents were 32% (OR = 0.68, p = .23, 95% CI
[0.37, 1.27]) less likely to be married. They were 22% (OR= 0.78, p = .33, 95% CI

[0.48,1.28]) less likely to view religion as somewhat important and their reaction to an
unintended pregnancy was 23% (p = .68, 95% CI [0.46, 3.29]) higher to be very upset
than the referent group.Although the odds of contraceptive use at sexual initiation among
sexually active African American women aged 18–24 increased with receipt of CSHE,
the odds were not significant. As such, I rejected the null hypothesis.
Table 11
Impact of Formal Sexual Health Education on Contraceptive Use at Sexual Initiation
Contraceptive use at sexual initiation
(No – Ref.) uOR
Una
djuste p
d
95% CI
Adjusted
aOR p 95% CI
Formal sexual health
education (Abstinence-
centered - Ref.)
Abstinence-plus 1.06
.90
[0.43, 2.63] 1.14 .80
[0.42, 3.09]
Comprehensive 1.29 .23 [0.86, 1.93] 1.38 .17 [0.87, 2.19]
Mother’s age at first birth (<18 -
Ref.)
18–19 0.66 .28 [0.31, 1.41] 0.55 .19 [0.23, 1.35]
20–24 0.97 .87 [0.68, 1.39] 0.86 .46 [0.58, 1.28]
≥25 1.03 .82 [0.79,
.35] 0.92
.60
[0.68, 1.26]
Yes Mother’s education (≤11th grade
- Ref.)
High school diploma/GED
2 years of college/associate
degree
Bachelor’s degree or higher
2.87
1.33
1.18
.01
.16
.75
[1.12,
[0.89,
[0.87,
6.42]
1.98]
1.61]
2.91
1.31
1.11
.02
.25
.58
[1.21,
[0.83,
[0.76,
7.01]
2.07]
1.62]
Married parents at participants’
birth (No - Ref.)
Yes 0.74
.
29
[0.43,
1.29] 0.68
.
23
[0.37, 1.27]
Importance of religion (Not
important - Ref.)
Very important 0.64
.
25
[0.30,
1.38] 0.49
.
09
[0.21, 1.12]
Somewhat important 0.86 .51 [0.55, 1.34] 0.78 .33 [0.48, 1.28]

Reaction to an unintended
pregnancy (Would not care -
Ref.)
Very upset 1.21 .69
[0.48,
3.03] 1.23
.
68
[0.46, 3.29]
A little upset 1.11 .65 [0.70, 1.77] 1.07 .78 [0.66, 1.74]
A little pleased 1.02 .89 [0.73, 1.43] 1.11 .95 [0.71, 1.43]
Very pleased 1.03 .85 [0.78, 1.36] 1.13 .43 [0.84, 1.52]
Research Question 3
With RQ3, I explored the association between the type of FSHE received and the
effectiveness of the contraceptive method selected at sexual initiation for sexually active
African American women aged 18–24. To answer RQ3, I used multinomial logistic
regression to determine the association between the type of self-reported FSHE received
(abstinence-centered, abstinence-plus, or comprehensive) and effectiveness of
contraceptive method selected (none, less effective, moderately effective, and highly
effective) at sexual initiation by sexually active African American women aged 18–24.
At sexual initiation, 50.6% (n = 121) of young women used a LECMs, with a high
percentage, 43.5% (n = 104) using MECMs (see Table 6). None (2.5%, n = 6) and
LECMs categories were combined, as were MECMs and HECMs (3.4%, n = 8)
contraceptive method categories as the percentages of none and HECMs were less than
5%. I did not include young women 25–29 years of age in the analysis due to the
percentage of the group being less than 5%. ACSHE and none–LECM categories selected
were the referent groups. ORs were used to measure the strength of the association with
the CIs set at 95%, and the critical p-value significance was .05.

According to Table 13, the odds of using a MECM to HECM was 48% (OR =
0.52, p = .18, 95% CI [0.20, 1.35]) less likely with receipt of APSHE and 16% (OR =
0.84, p = .4, 95% CI [0.55, 1.27]) less likely with receipt of CSHE. Young women who
used MECMs to HECMs were at 65% (OR = 1.65, p = .22, 95% CL [0.75, 3.64]) higher
odds of being born to a mother 18–19-years old was 58% (OR = 0.42, p = .05, 95% CI
[0.18, 1.00]) less likely to have a high school diploma or GED, which was significant. It
was 39% (OR = 1.39, p = .28, 95% CI [0.76, 2.52]) more likely that the participant’s
parents were married at their birth and was 34% (OR = 1.34, p =.45, 95% CI [0.63, 2.86])
more likely to view religion as important. They were 5% (OR = 1.05, p = .7, 95% CI
[0.80, 1.38]) to be very pleased if they experienced an unintended pregnancy.
The odds of selecting a MECM to HECM at sexual initiation among sexually active
African American women aged 18–24 did not increase with receipt of CSHE. As such, I
failed to reject the null hypothesis.
Research Question 4
For RQ4, I explored the association between the type of FSHE received and the
effectiveness of the contraceptive method primarily selected by sexually active African
American women aged 18–24 at intercourse within the past 12 months. To answer RQ4, I
used multinomial logistic regression to determine the association between the selfreported
type of FSHE received (abstinence-centered, abstinence-plus, or comprehensive) and
effectiveness categories of the contraceptive method primarily selected (none, less
effective, moderately effective, and highly effective) by sexually active African American

women aged 18–24 at last intercourse within the past 12 months. ACSHE and no use of
contraception were referent groups. ORs were used to measure the strength of the
association with the CI set at 95%, and the critical p-value significance was .05.
None (n = 100, 41.3%; see Table 6) was the contraceptive effectiveness category
African American women aged 18–24 primarily selected during intercourse for the last
12 months. Young women used LECMs (n = 62, 25.6%), MECMs (n = 58, 24%) and
HECMs (n = 22, 9.1%) contraceptive effectiveness categories, respectively. According to
Table 14, young women who used LECMs were 2.05 (OR = 2.05, p = .27, 95% CI [0.57,
7.41]) times more likely to have received receipt of APSHE and 18% OR = 1.18, p = .58,
95% CI [0.66, 2.11]) more likely to have received CSHE. Young women who selected
LECMs over the last 12 months were 10% (OR = 1.10, p = .68, 95% CI [0.69, 1.76])
more likely to be born to mothers 20–24 years old who were 1% (OR = 1.01, p = .95,
95% CI [0.66, 1.57]) more likely to have earned a baccalaureate degree and 2.11 (p = .05,
95% CI [0.99, 4.49]) times more likely to be married at the participants’ birth, which was
significant. The odds were 12 % (OR = 1.12, p = .7, 95% CI [0.64, 1.96]) more likely that
they viewed religion as somewhat important and 4.96 (p = .03, 95% CI [1.18, 20.76])
times more likely that they would be very upset if an unintended pregnancy occurred,
which was significant.
Within the previous 12 months, young women were less likely to primarily select
MECMs if they received APSHE (OR = 0.66, p = .5, 95% CI [0.20, 2.29]) or CSHE (OR

= 0.75, p = .2, 95% CI [0.44, 1.27]) (see Table 14). They were 64% (OR = 1.64, p = .06,
95% CI [0.98, 2.74]) more likely to be born to mothers aged 20–24-years of age who
were 68% (OR = 0.32, p = . 05, 95% CI [0.10, 1.02]) less likely to have a high school
diploma or GED, which was significant. The odds were 17% (OR = 1.17, p = .58, 95%
CI [0.67, 2.04]) more likely that they viewed religion as somewhat important and 15.39
(p = .01, 95% CI [1.18, 130.86]) times more likely to be very upset if an unintended
pregnancy occurred, which was significant.
The odds of primarily selecting a HECM for intercourse over the last 12 months
increased by 18% (OR = 1.07, p = .7, 95% CI [0.50, 2.85]) if young women received
CSHE. The odds increased, 7% (OR = 1.07, p = .98, 95% CI [0.15, 7.83]), with receipt of
APSHE. They are 42% (OR = 1.42, p = .3, 95% CI [0.73, 2.78]) more likely to be born to
mothers 20–24years old who were 63% (OR = 0.37, p = .21, 95% CI [0.08, 1.75]) less
likely to have high school diploma or GED, and 76% (OR = 1.76, p = .3, 95% CI [0.60,
5.18]) more likely to have been married at the participants’ birth. The odds were 4.03 (p =
.1, 95% CI [0.75, 21.55]) times more likely that they viewed religion as important and
2.56 (p = .2, 95% CI [0.61, 10.69]) times more likely that they would be very upset if an
unintended pregnancy occurred. Receipt of APSHE nor CSHE increased the odds of
selecting a moderately to highly effective contraceptive as the primary contraceptive
method for the past 12 months among sexually active African American women aged 18–
24. As such, I failed to reject the null hypothesis.

Summary
In Chapter 4, I reported results of a quantitative cross-sectional analysis of the
2015–2017 NSFG that explored the impact that receipt of the various forms of FSHE
(abstinence-centered, abstinence-plus, and comprehensive) may have on the age of sexual
initiation, the contraceptive use at sexual initiation, use of more effective contraceptives
at sexual initiation, and use of more effective contraceptives as the predominate method
during sexual encounters over the previous 12 months among African American women
aged 18–24 who have sex with men. According to the data analysis, the odds of being in
an older category for the age of sexual initiation among sexually active African American
women aged 18–24 increased with APSHE. It increased with CSHE when compared to
ACSHE, the referent group. However, the odds were not significant, and the age of
initiation was still within a normative age range. The odds of contraceptive use at sexual
initiation among sexually active African American women aged 18–24 increased with
receipt of CSHE; however, the odds were not significant. The odds of selecting a
moderately to highly effective contraceptive at sexual initiation among sexually active
African American women aged 18–24 did not increase with receipt of CSHE. The receipt
of APSHE nor CSHE increased the odds of selecting a moderately to highly effective
contraceptive as the primarily selected contraceptive method for the past 12 months
among sexually active African American women aged 18–24.
Chapter 5 includes an interpretation of the analysis results from Chapter 4 and the
limitations of this study and its implications and recommendations for applying the

results to improve the provision of FSHE among African American young women aged
18–24. Chapter 5 includes a comprehensive overview of this research study, a description
of my plans for the future use of study data and results. It also includes possibilities for
continued research on this topic.
Chapter 5: Discussion, Conclusion, and Recommendations
Introduction
The purpose of this quantitative cross-sectional analysis of the 2015–2017 NSFG
was to ascertain the impact receipt of FSHE (knowledge; main independent variable) on
sexual initiation and contraceptive selection and use (dependent variables) among African
American women aged 18–24 who have sex with men. I used descriptive statistics,
logistic regression, and multinomial logistic regression to evaluate the research questions
and accept or reject the hypotheses. Understanding associations between these variables
may lead to better provision of public health services that may lead to delayed sexual
initiation, as well as increased, consistent and proper use of preference and intention
matched methods, reducing occurrences of unplanned pregnancies in this population.
Unintended pregnancy can lead to significant emotional, social, health, and financial
complications, which in turn, may perpetuate cycles of disadvantage experienced by
vulnerable populations, especially in terms of racial disparities in morbidity and mortality
across the. This analysis may lead to positive social change by highlighting the
importance of the provision of FSHE to African American young women aged 18–24
who have sex with men. African American young women may apply knowledge and

skills learned to prevent unintended pregnancies, and by extension, may have fewer
adverse maternal and child public health outcomes.
The goal of FSHE is to prepare young adults to be sexually healthy (Santelli et al.,
2017). A literature review provided evidence that racial and ethnic disparities involving
contraceptive knowledge exist with an association shown between less knowledge and
less contraceptive use. Knowledge and attitudes formed about contraception during
adolescence may persist throughout life (Guzzo & Hayford, 2018). Receipt of FSHE was
lower among individuals with lower socioeconomic status, who were African American,
and whose mothers had lower educational attainment (Lindberg & Maddow-Zimet,
2012). African American young women report earlier sexual initiation and are more
likely to experience unwanted or mistimed pregnancy than their peers (Moilanen et al.,
2018). Contraceptive knowledge is typically lower, and unintended pregnancies are
higher in 18–19-year-old women (Wu et al., 2016). Dehlendorf et al. (2014) found that
African American women under the age of 19 were less likely than Caucasian women to
use IUDs or implants, while African American young women between the ages of 20–24
were slightly more likely to use IUDs and implants than Caucasian women.
For the current study, I analyzed data from the 2015–2017 NSFG to determine the
impact of FSHE on age of sexual initiation, use of contraceptive at sexual initiation, use
of more ECM at sexual initiation, and use of more ECM as the predominate method
during sexual encounters during the 12 months before the survey among African

American women aged 18–24. I compared the impact based on the receipt of ACSHE
(referent group) with that of APSHE and CSHE. Most young women surveyed
experienced sexual initiation between 14–17 years of age (70.3%) compared to the ≤13
years of age referent group (9.1%; see Table 6). The results of my study indicate that the
odds of experiencing sexual initiation in the 14–17-year-old initiation category were 34%
higher (OR = 1.34, p = .73; see Table 11) if young women received APSHE and 22%
higher (OR = 1.22 p = .61) if they received CSHE, compared to those who received
ACSHE. The odds of being in an older category (18–19) for the age of sexual initiation
were 5% higher (OR = 1.05, p = .98) if young women received APSHE and 5% lower
(OR = 0.95, p = .98) if they received CSHE, compared to those who received ACSHE.
The odds of contraceptive use at sexual initiation increased by 14% (OR = 1.14, p = .8;
see Table 12) with receipt of APSHE and 38% (OR = 1.38, p = .17), compared to those
who received ACSHE. The odds of selecting a MECM to HECM over a none to less
effective category at sexual initiation did not increase with receipt of APSHE (OR = 0.52,
p = .18; see Table 13) nor with CSHE (OR = 0.84, p = .4).
The receipt of APSHE nor CSHE increased the odds of selecting a MECM to
HECM as the primarily selected contraceptive method during the 12 months before the
survey among sexually active African American women aged 18–24. Young women who
used LECMs were 2.05 times more likely (OR = 2.05, p = .27; see Table 14) to have
received receipt of APSHE and 18% more likely (OR = 1.18, p = .58) to have received
CSHE. Young women were less likely to primarily select MECMs if they received

APSHE (OR = 0.66, p = .5) or CSHE (OR = 0.75, p = .2). The odds of primarily selecting
a HECM for intercourse over the last 12 months increased by 18% (OR = 1.07, p = .7) if
young women received CSHE. The odds increased, 7% (OR = 1.07, p = .98), with receipt
of APSHE.
Interpretation of the Findings
Formal Sexual Health Education
FSHE promotes safer sexual behaviors for young adults, including delayed sexual
initiation and increased and correct contraceptive usage beginning at first sexual
encounter (Lindberg & Maddow-Zimet, 2012). African American women aged 18–24 are
at a higher risk for unintended pregnancy due to nonuse, inconsistent, or improper use of
contraception, as well as failure to use dual contraceptive methods (Craig et al., 2014).
Shepherd et al. (2017) found that African American adolescents who received CSHE had
more favorable attitudes about contraception, demonstrated an increase in consistent
contraception usage, and reported less teen pregnancy and vaginal intercourse,
highlighting the importance of early CSHE. Therefore, knowledge and attitudes formed
about contraception during adolescence may persist throughout life. This suggests the
need for increased CSHE among African American young women who have poorer
sexual reproductive health outcomes, including higher rates of unintended pregnancy and
STIs.
Based on my analysis of the 2015–2017 NSFG, I found that of the 242 African
American women aged 18–24 included in this study, 63.2%; received CSHE. Twentyfour

percent still received some information about contraception via APSHE, 12.8% receiving
FSHE that was ACSHE. Of the young women surveyed, 61.6% were born to unwed
mothers, of which 36.8% only earned a high school diploma or GED. At participant’s
birth, 29.7% of their mothers were 20–24 years old at their births, while
27.2% were under 18.
Formal Sexual Health Education and Sexual Initiation
Sexual initiation, considered a critical life transition event, is a significant
milestone towards adulthood as young adults accept increasing responsibility for their
decisions. The mean age of sexual initiation among American women is approximately
17, with 15% having had their first heterosexual vaginal intercourse experience before
their 15th birthday (Guttmacher Institute, 2018; Magnusson et al., 2015). African
American young women report earlier sexual initiation (Moilanen et al., 2018). Current
national norms for the U.S. consider sexual initiation that occurs before 15 as early,
between 15 and 19 as normative, and after 19 as late (Golden et al., 2016). The normative
range for this study decreased to age 14, as African American young women report earlier
sexual initiation (Moilanen et al., 2018).
Based on the findings for this study, I could not reject the null hypothesis for
RQ1. This finding aligns with and supports results from the literature that found that
receipt of FSHE had little impact in increasing the age of sexual initiation for African
American young women aged 18–24 past a normative age. Young women were 34%
more likely to experience normative sexual initiation with receipt of APSHE and 22%

more likely with receipt of CHSE (see Table 11). They were, however, only 5% more
likely to wait until age 18–19 to have sexual intercourse with receipt of APSHE and were
5% less likely to wait with receipt of CSHE. The findings for RQ1, although
nonsignificant, are still important because they suggest that FSHE received may provide
knowledge that consensual sexual behavior can be healthy, normative, and provides
young adults with the tools needed to make well-informed, healthy decisions around
sexual experiences (Bourke et al., 2014; Golden et al., 2016).
The findings, when viewed through the lens of the RAA, suggest that
demographics and norms may have also played a role in the age of sexual initiation with
young women within the normative initiation range. African American women are
exposed to higher rates of teen and single parenthood, earlier sexual initiation, and use
contraception less effectively (Barber et al., 2015). Key findings from my analysis
included that young women within the normative initiation range were more likely born
to unwed mothers (aOR = 1.04, p = .95; see Table 11), with only a high school diploma
or GED (aOR = 8.78, p = .01), and under the age of 24 (aOR = 1.45, p = .64). Young
women who delayed initiation until 18–19 years old were more likely to be born to wed
mothers (aOR = 1.40, p = .63), who had a high school diploma or GED (aOR = 7.34, p
= .02), and under the age of 24 (aOR = 2.25, p = .8). Young women in the 18–19 year old
initiation age group were more likely to view religion as very important (aOR = 5.07, p =
.06) than their 14–17 year old counterparts (aOR = 1.81, p = .42).

Formal Sexual Health Education and Contraceptive Selection and Use
Despite most young adults believing that pregnancy should be planned (86-94%),
more than 70% of pregnancies among unmarried women aged 18–24 are unplanned and
likely due to nonuse or inconsistent contraceptive use (Kornides et al., 2015). Paterno et
al. found in their 2017 study that among women aged 20–24, 11.4% to 13% used no
contraceptive method. This number was higher among African American participants,
despite 60% of African American women aged 18-24 who believed pregnancy planning
is important, and 80% desired to avoid pregnancy (Paterno et al., 2017). The findings of
this current study align with their study and emphasize the need for more research around
contraceptive usage among African American women aged 18–19, as, in my analysis,
32.5% did not use contraception at sexual initiation (see Table 6). Among the 67.5% of
young women who self-reported contraceptive use at sexual initiation, 50.6% used a
LECMs, and 43.5% (n = 104) using MECMs. None (2.5%) and LECM categories were
combined, as were MECMs and HECMs (3.4%) categories as the percentages of none
and HECMs were less than 5%. Within the last 12 months, the effectiveness category
selected shows that more young women (41%) opted not to use contraception. Among
those that used contraceptives, LECMs (25.6%) and MECMs (24%) were predominately
used. The use of HECMs (9.1%) methods was scarce. The findings from my study align
with current literature as LARC use remains low in young women despite being one of
the most effective forms of pregnancy prevention (Logan et al., 2018). Fewer than 5% of
15–19 year olds select LARCs as their preferred contraception method, and the usage

among young African American women remains lower than in other racial/ethnic groups
(Coates et al., 2018; Logan et al., 2018).
The results of RQ2, although nonsignificant, demonstrate that contraceptive use at
sexual initiation increased by 14% with receipt of APSHE (OR = 1.14, p = .8) and by
38% with CSHE (OR = 1.38, p = .17) compared to those who received ACSHE (see
Table 12). While FSHE increased use at sexual initiation, odds of selecting a MECM to
HECM at sexual initiation were 48% less likely with receipt of APSHE as well as 16%
less likely with receipt of CSHE (see Table 13). The results from RQ3 suggest there is a
need for more culturally competent contraceptive education to reduce misconceptions
about long-term contraceptive methods. African American women who perceive negative
peer norms involving contraceptive use are more likely to have inconsistent contraceptive
usage and utilize LECMs (Crosby et al., 2013). Compared to Caucasian and Hispanic
women, African American women are more likely to report concerns regarding side
effects of contraceptive methods as their rationale for not using contraception (Kornides
et al. 2015). Contraception use, specifically LARC use, might be increased by providing
young women more information on effectiveness, side effects, affordability, and ease of
use (Kornides et al., 2015).
Similar usage persists into the predominate contraceptive method used within the
last 12 months. My analysis of the data found that young women who received APSHE
were more likely to select LECMs (aOR = 2.05, p = .27) compared to MECMs (aOR =
0.66, p = .5), and HECMs (aOR = 1.07, p = .95) methods (see Table 14). Young women

who received CSHE were more likely to equally select LECMs (aOR = 1.18, p = .58) and
HECMs (aOR = 1.18, p =.7) methods compared to MECMs (aOR = 0.75, p = .2)
methods. It is important to note that within the last 12 months, HECMs were used as
frequently as LECMs among recipients of CSHE. These findings align with those found
by Dehlendorf et al. (2014), who noted that African American women between the ages
of 20–24 were slightly more likely to use IUDs and implants than Caucasian women.
Logan et al. (2018) found that LARC use in young women nearly doubled at the age of
24. Although the results of RQ4 show that use of HECMs is still low, it suggests that
CSHE may be an important factor to increase use in this population by addressing
negative attitudes and beliefs about LARCs stemming from social norms, the knowledge
gained through vicarious experiences, as well as knowledge of institutional racism and
medical mistrust.
The findings, when viewed from the lens of the RAA framework, suggest that
FSHE received shaped attitudes and norms by providing knowledge regarding
contraceptive intention, starting at initiation, and influences the selection of effectiveness
category. In my analysis, young women predominately used LECMs, which may have
been impacted by demographics and norms. Young women who used contraception at
sexual initiation were less likely to be born to mothers 18–19 years old (aOR= 0.55, p
= .19; see Table 12). Most mothers had at least a high school diploma or GED (aOR =
2.91, p = .02), but were less likely to be married (aOR = 0.68, p = .23). Young women

who used contraception at sexual initiation were also less likely to view religion as very
important (aOR= 0.49, p = .09). Young women with mothers 18–19 years old (aOR=
1.65, p = .22) and married (aOR= 1.39, p = .28) at their birth were more likely to use
MECMs to HECMs at sexual initiation, which suggests a protective factor (see Table 13).
They were less likely born to mothers who only had a high school diploma or GED (aOR
= 0.42, p = .05). Young women who selected MECMs to HECMs at sexual initiation
were more likely to view religion as very important (aOR = 1.34, p = .28).
According to my analysis of the data, when selecting a primary contraceptive method
over the last 12 months, young women born to an older mother selected more effective
methods with most selecting MECMs (aOR = 1.64, p = .06) or HECMs (aOR = 1.42, p
= .3; see Table 14). They also were less likely born to women who earned only a high
school diploma or GED (moderately effective: (aOR = 0.32, p = .05) and highly effective
(aOR = 0.37, p = .21). Young women born to married parents selected LECMs (aOR =
2.11, p = .05), which suggests a family-minded norm as they also reported they would be
a little pleased with an unintended pregnancy (aOR = 1.68, p = .04).
Limitations
The purpose of this quantitative cross-sectional analysis of the 2015–2017 NSFG
was to explore the receipt of FSHE and the impact it may have on sexual initiation,
contraceptive use, and contraceptive selection among African American women aged 18–
24 who have sex with men. As a secondary analysis of data, a limitation of this research
may be possible nonsampling errors due to the cross-sectional nature of the NSFG and

primary data collection. As such, I am unable to correlate the extent to which knowledge
impacts contraceptive selection, nor can I draw causal inferences from these
crosssectional data. Another limitation of this study is the use of self-reported data, which
is subject to participant recall and interviewer biases as well as over- and under-reporting.
The majority of the NSFG responses occurred via ACASI to reduce limitations and
biases.
The sample size was also a limitation of this study. Although the oversampling of
the study population occurred to include more African American women, the sample size
was still small; only 1,355 of the 5,554 women interviews were conducted with
nonHispanic Black women. The sample size for this study was further limited because a
subsample used contained 499 sexually active, African American women aged 18–24
who have sex with men. Data cleaning yielded a final sample size of 242 sexually active,
African American women aged 18–24 who have sex with men. This small sample size
highlights the need for more robust, targeted studies among African American women
instead of limited qualitative and small studies focusing on nonuse or large surveys
providing percentages of African American women respondents.
Access to the data needed to complete this study was another limitation.
Requirements for FSHE vary by state; therefore, the region of residence was a key topic
in my initially planned study. The NSFG includes a restricted variable, REGION, that
identifies a respondent’s region of residence. When I started this research study, the
REGION variable for the 2015–2017 NSFG was listed on the NSFG website as available

free of charge, with access grant via an encrypted email with a written request and
submission of confidentiality forms. After submitting a written request for access to the
REGION variable, the variable was changed to a fee-based model with limited access,
which made the inclusion of this variable cost-prohibitive.
Recommendations
Practice Recommendations
The goal of FSHE is to prepare young adults to be sexually healthy (Santelli et al.,
2017). Despite concerns, there is no evidence to support that receipt of CSHE is
associated with an earlier sexual initiation, increased risk-taking, or poorer sexual
reproductive health outcomes. CSHE, which occurs before sexual initiation, leads to
delayed onset of sexual initiation; greater use of more effective contraception, especially
at first sexual encounter; and healthier sexual relationships (Jaramillo et al., 2017;
Lindbery & Maddow-Zimet, 2012). The key results of my data analysis demonstrate that
receipt of FSHE has an impact on sexual initiation and contraceptive use and selection
among African American women aged 18–24. APSHE and especially CSHE lead to
delayed sexual initiation, increased contraceptive use at sexual initiation, and more
effective contraceptive use long term. ACSHE, however, does not have a significant
impact on sexual initiation or sexual behaviors and may place young people at increased
likelihood of pregnancy and STIs once they become sexually active by overlooking or
downplaying the benefits of contraception (Boyer, 2018).

Young women, especially those of color, may be at risk of not receiving
highquality family planning care (Dehlendorf et al., 2014). This disparity may contribute
to healthcare disparities, disengagement from healthcare interactions, and perpetuated
institutional mistrust (Gomez & Wapman, 2017). Based on the results of this study, my
recommendation is an increased provision of CSHE that is culturally aware and
responsive for African American young women in educational, public health, and medical
settings. Reproductive trends in contraceptive use among African American women may
be impacted by a reproductive history of medical and reproductive abuse. As such, CSHE
needs to be tailored to address social and cultural norms to offset vicarious experiences
and misperceptions. CSHE must be tailored to address side-effects and perceived impacts
on fertility specifically. CSHE may help reduce medical mistrust, misperceptions about
contraceptive use, especially LARCs, and help African American young women find a
contraceptive method best matched to their pregnancy intentions. By being aware of
reproductive justice issues, public health sexual health educators and practitioners may be
better able to address concerns raised by African American young women.
Clinicians are more likely to recommend LARCs to low-income women of color
compared to their Caucasian counterparts (Gomez & Wapman, 2017). This type of
provider coercion was seen particularly with patients deemed high-risk, despite their
contraceptive preferences (Morse & Moos, 2018). Provider coercion occurred despite
income, with well-educated patients describing feelings of pressure to be compliant,
discomfort with expressing their opinions and views, and the need to accept provider

recommendations (Joseph-Williams et al., 2014; Sacks, 2017). Public health educators
can fill this communication gap through the provision of CSHE that considers African
American young women’s long-term goals as well as pregnancy intentions. Sexual health
interventions should be tailored to promote favorable attitudes and social norms towards
contraception as young women with positive normative beliefs are more likely to use
contraception. Such efforts might include integrating reproductive planning into all
primary care encounters where questions and information regarding pregnancy intention
as well as effectiveness, ease of use, affordability, and satisfaction with current
contraceptive methods are explored (Kelly, 2014; Kornides et al., 2015). This would
provide the opportunity for public health and clinical practitioners to work together to
improve the reproductive health of African American young women. This joint
partnership would allow public health educators the ability to focus on reducing the
number of sexual partners, increasing the use of hormonal contraception, increase the use
of dual contraceptive methods, and use of LARCs (Buhi et al., 2010; Kornides et al.,
2015). Doing so would allow clinicians to focus on clinical services.
Research Recommendations
A gap in research involving reproductive and contraceptive disparities in African
American young women persists. Targeted research that aggressively and primarily
focuses on African American young women is needed. More extensive quantitative
studies are required to determine the impact of FSHE on reproductive and contraceptive
outcomes, especially based on the region of residence. More nuanced qualitative studies

are needed to explore the effect that background factors, including social norms and
networks, play on reproductive and contraceptive outcomes among African American
young women. My research plans include an exploration of FSHE and reproductive and
contraceptive outcomes among African American young women attending historically
Black colleges and universities. Addressing this gap in literature may lead to the
development of interventions designed to prevent unintended pregnancies through
increased consistent, preference, and intention matched contraceptive use. Well-designed
interventions that focus on CSHE may improve maternal health and reduce adverse birth
outcomes, all of which are public health concerns in young African American women.
An additional plan may include an exploration into the implicit and explicit biases
African American young women experience during family planning.
Implications
African American young women report earlier sexual initiation, use of LECMs,
and are more likely to experience an unwanted or mistimed pregnancy than their peers
(Golden et al., 2016; Lanier et al., 2018; Moilanen et al., 2018). CSHE may have a
protective influence on early sexual initiation (Bourke et al., 2014). Unintended
pregnancy may lead to disparities in delayed prenatal care, reduced breastfeeding,
depression, delivery of infants with low birth weight and birth defects, as well as reduced
average income compared to other women (Carter et al., 2013; James & Rashid, 2013;
USDHHS, 2019). Infants born from unintended pregnancies experience increased risk of
poor mental, physical, and behavioral health in adolescence, as well as lower educational

attainment themselves (James & Rashid, 2013; USDHHS, 2019). Findings from my
study demonstrate that increasing African American young women’s access to FSHE,
which highlights modern contraceptive methods, may mitigate these factors.
Positive Social Change
The key findings of my data analysis may lead to positive social change by
providing public health educators and practitioners with a better understanding of the
impact of FSHE on contraceptive use, contraceptive selection, and sexual initiation
among African American young women. APSHE and especially CSHE lead to delayed
sexual initiation, increased contraceptive use at sexual initiation, and more effective
contraceptive use long term. ACSHE, however, does not have a significant impact on
these behaviors as it withholds essential information to make healthy sexual decisions.
An increased understanding of this impact of FSHE will help public health educators and
practitioners provide African American young women with the required knowledge and
skills needed to delay sexual initiation as well as consistently and properly use preference
and intention matched methods. African American young women may apply the
knowledge and skills learned to prevent unintended pregnancy and may decrease adverse
maternal and child associated public health outcomes. Doing so may positively impact the
socioeconomic status of African American young women and resulting children, which
may improve associated social, educational, and public health outcomes for both
populations.

Conclusion
Through this quantitative, cross-sectional analysis of the 2015–2017 NSFG, I
explored receipt of FSHE and the impact it had on sexual initiation, contraceptive use and
selection among African American women aged 18–24 who have sex with men. Key
findings from this study include that among sexually active African American Women
aged 18–24, neither APSHE nor CSHE extended the age of sexual initiation past a
normative age. Contraceptive use at sexual initiation increased with receipt of CSHE, and
the odds of selecting a MECM to HECM at sexual initiation did not increase with receipt
of CSHE. The receipt of APSHE, as well as CSHE, did not increase the odds of selecting
a MECM to HECM as the primarily selected contraceptive method for the past 12 months
among sexually active African American women. CSHE, however, did lead to young
women selecting HECMs at similar odds to LECMs.
The results of this study add to the literature on the impact of FSHE on the age of
sexual, contraceptive use, and contraceptive selection among African American young
women aged 18–24, which is a public health concern as they impact on unplanned and
mistimed pregnancy. Understanding contraceptive selection among African American
young women may assist public health and clinical practitioners with a better
understanding of the impact of FSHE on contraceptive use and selection and sexual
initiation among African American young women. The key findings of this analysis may
lead to positive social change by providing African American young women with the
required knowledge and skills needed to delay sexual initiation as well as consistently and

properly use preference and intention matched methods, reducing the occurrence of
unplanned pregnancy in this population. The key findings of this analysis may be used to
increase the provision of culturally competent public health services, such as sexuality
and reproductive education, family planning, and contraceptive counseling, which may
increase the selection and consistent use of contraceptive methods best fit for
reproductive intentions, reduce usage failures and improve birth-related outcomes.

