


Introduction Symptoms and Causes of Food-Borne Illness
Chapter Overview
This chapter provides the introduction and background to the study, including the
statement of the problem, purpose, research questions, hypotheses, theoretical basis,
nature, operational definitions, significance, scope, delimitations, and limitations of the
study.
Introduction
In the United States, the restaurant industry’s economic impact is estimated at
$1.8 trillion, with annual sales of $660 billion each year and 13.1 million employees,
representing 10% of the U.S. workforce (National Restaurant Association [NRA], 2013).
Employment in the restaurant industry is expected to increase to 14.4 million by 2023
(NRA, 2013). In Georgia, there are an estimated 378,200 people employed in the
restaurant industry, making up 10% of Georgia’s workforce (Georgia Restaurant
Association [GRA], 2013). In 2011, there were a total of 16,295 eating and drinking
establishments in Georgia. Restaurants in Georgia were estimated to register $16 billion
in sales in 2013 (GRA, 2013).
Annually, there are estimated to be 76 million cases of food-borne illnesses in the
United States, which include 325,000 hospitalizations and 5,000 deaths (U.S. Food and
Drug Administration [FDA], 2009c). Sixty-five percent of food-borne illness outbreaks in
U.S. restaurants were linked to infected restaurant employees, who can directly transmit
pathogens that cause food-borne illness in consumers (FDA, 2009c). There are many
different microorganisms including bacteria, viruses, and parasites that can cause

foodborne illness. Eight pathogens are known that cause the vast majority of illnesses,
hospitalizations, and deaths: Norovirus, Salmonella, Clostridium perfringens,
Campylobacter spp., Staphylococcus aureus, Toxoplasma gondii, Listeria
monocytogenes, and E. coli (STEC) 0157 (Card, Joatis, Tafazol, & Magnuson, 2011;
Centers for Disease Control and Prevention [CDC], 2013). Norovirus, Salmonella,
Clostridium perfringens, Campylobacter spp., and Staphylococcus aureus are the top five
pathogens that contribute to domestic food-borne illness; Salmonella, Norovirus,
Campylobacter spp., Toxoplasma gondii, and E. coli (STEC) 0157 are the top five
pathogens that contribute to domestic food-borne illness resulting in hospitalization; and
Salmonella, Toxoplasma gondii, Listeria monocytogenes, Norovirus, and Campylobacter
spp. contribute to domestic food-borne illness resulting in death (Card, Jonaitis, Tafazoli,
& Magnuson, 2011; CDC, 2013).
Symptoms and Causes of Food-Borne Illness
Food-borne illness may be contracted by eating food that has been contaminated
by a bacterial agent, a virus, or parasite, but also can be caused by a chemical or physical
hazard (CDC, 2013; Foodsafety, 2013a). Symptoms associated with food-borne illness
usually depend on the microorganism causing the disease but often include abdominal
cramps, vomiting, nausea, fever, diarrhea, and dehydration (Foodsafety, 2013a). In
general, symptoms usually develop within 12 hours of exposure and can last for one or
more days; however, the onset and duration of symptoms can vary depending on the
microorganism (Yarrow, Remig, & Higgins, 2009). Most individuals will recover with no
long-term effects, but for some, the effects can be detrimental. Long-term effects include
kidney failure, chronic arthritis, brain and nerve damage, and/or death (Foodsafety,

2013a).
Microorganisms are more common than physical and chemical hazards,
accounting for 90% of food-borne illnesses (Foodsafety, 2013a). There are many ways in
which a microorganism can contaminate food, such as coughing and sneezing by an
infected individual, undercooked food, and inadequate hand-washing (Foodsafety,
2013a). For bacteria to cause a food-borne illness, the bacteria have to multiply to large
numbers and need certain conditions such as food, acidity, temperature, time, oxygen, and
moisture. Food provides bacteria with the nutrients and energy to survive; foods that are
neutral to slightly acidic provide the best environment for bacterial growth. In
temperatures between 41°F and 135°F, bacteria grow rapidly; bacteria grow even more
rapidly in temperatures between 70°F to 120°F. The more time bacteria have in the
temperature danger zone, the better opportunity the bacteria have to multiply to unsafe
levels. Some bacteria require oxygen, whereas others do not. Bacteria grow well in foods
that contain high levels of moisture (FDA, 2012).
Viruses and parasites require a host to live and multiply. While viruses do not
grow on food, food serves as a vehicle for viruses, and a virus can remain infectious and
cause food-borne illness if the contaminated food is eaten. Typically, the fecal-oral route
is the mode of transmission of viruses. As viruses are not destroyed by normal cooking
temperatures, it is extremely important to practice good personal hygiene (FDA, 2012).
Parasites are transmitted from host to host (e.g., animal to human, human to human) by
consuming food that has been contaminated by feces from an infected individual or
animal (Foodsafety, 2013b; FDA, 2013). In size, parasites vary from tiny single-celled
microorganisms to worms that are visible to the eye. Preventive activities such as

washing hands after using the bathroom, before handling food, and after handling animals
and cooking food to the proper temperature are significant in preventing food-borne
illness (Foodsafety, 2013b, FDA, 2013).
Georgia Food Rules and Regulations
According to Georgia Food Service Rules and Regulations Chapter 290-5-14,
food service establishments must have at least one person designated as a Certified Food
Safety Manager (CFSM). To obtain certification as a CFSM, one must successfully
complete and pass a professional food safety training examination that is accredited by
the Conference for Food Protection or another agency that conforms to national standards
and certifies individuals (Georgia Department of Public Health, n.d.). During operating
hours of an eating establishment, the person in charge is usually the CFSM or a person
designated by the CFSM as in charge in his or her absence. Such an individual is are
responsible for overseeing food preparation and safety, ensuring that the objectives of the
rules and regulations of Chapter 290-5-14-.03(3)(d) are being met by (a) supervising and
instructing employees on techniques related to food handling and maintenance, (b)
offering training for employees in food safety, (c) communicating with health officials on
the effectiveness of programs for employees, and (d) evaluating food service employee
training needs and recommending training in food safety as they see fit. The CFSM or
designee has the knowledge and skills to recognize risk factors that may contribute to
food-borne illness and knows what preventive measures and actions need to be taken
(Georgia Department of Public Health, n.d.; FDA, 2009b).
ServSafe® is a program developed by the National Restaurant Association and
provides training in food safety, exams, and educational materials for managers working

in food service. Food service managers can earn their CFSM certificate by taking and
passing the exam offered by the program. The program is recognized by federal, state,
and local jurisdictions and is accredited by the Conference for Food Protection and
American National Standards. The program trains managers in how to identify risk
factors and implement food safety practices in their facilities. The certification course is
16 hours in length and covers concepts such as the importance of food safety, personal
hygiene, time and temperature control, cross contamination, proper cleaning and
sanitation of equipment, safe food preparation, receiving and storing food properly,
Hazard Analysis and Critical Control Points (HACCP), and food safety regulations. A
minimum score of 75% is needed in order to obtain a CFSM certification, which is valid
for 5 years (ServSafe, 2013).
Background
In the United States, regulatory agencies such as local, county, and state health
departments conduct health inspections of food handling facilities. The primary objective
of health inspections is the prevention of food-borne illness; this is accomplished by
control measures such as demonstration of knowledge (e.g., compliance with code,
presence of a certified food safety manager, food safety questions answered correctly),
implementation of employee health policies, hands as a vehicle of contamination,
monitoring of time/temperature relationships, and consumer advisories (FDA, 2009b).
Health inspectors perform inspections at restaurants to ensure that they are in compliance
with health and sanitation regulations designed to ensure safety of consumers and food
employees; however, food safety inspections alone have not been effective in decreasing
critical violations (Cruz, Katz, & Suarez, 2001; Jones, Pavlin, LaFleur, Ingram, &

Schaffner, 2004; Newbold, McKeary, Hart, & Hall, 2008; Phillips, Elledge, Basara,
Lynch, & Boatright, 2006). Food service workers are taught how to safely prepare and
handle food; not being properly trained on food safety can lead to food being mishandled,
which can increase risk factors for food-borne illness (Wotecki & Kineman, 2003).
Kassa, Silverman, and Baroudi (2010) examined food safety inspections and
compared the violations of facilities that had used a CFSM to those that had not. The
results revealed that the type of food safety training a CFSM received may have an effect
on violations. Because the majority of training focuses on theoretical concepts, the
authors suggested that training should turn toward a more hands-on approach. The type of
facility may also play a role in the number of violations. Jones et al. (2004) examined
inspection reports statewide from Tennessee and suggested that there were an array of
factors that influenced food safety inspections in preventing food-borne illness and that
training might modify some of the factors. DeBess, Pippert, Angulo, and Cieslak (2009)
surveyed food service workers in Washington County and Marion County, Oregon; the
data obtained from the surveys revealed that recertification is needed to reinforce food
safety. Cates et al. (2009) looked at the effectiveness of food safety training and
certification in restaurants located in Iowa and found that certain risk factors may be
controlled by having a Certified Kitchen Manager (CKM) but that training and
certification must be kept current to have a positive influence on risk factors. Green and
Selman (2005) collected data from food workers on their beliefs regarding factors that
impact food safety and food practices. The findings suggest that there are many factors
that have an impact on safe food handling practices and indicate that education is
important but not enough to ensure food safety. Education must also address other factors

that may have an impact on safe food handling practices, such as management and
environmental constraints.
Problem Statement
There is evidence in the literature that restaurants are the precursor of many
reported food-borne illnesses (Olsen, MacKinon, Goulding, Bean, & Slutsker, 2000). In a
study from 1993-1997 by Olsen et al. (2000), the researchers found that 27% to 33% of
food-borne illness outbreaks were associated with poor personal hygiene of food
handlers. Guzewich and Ross (1999) found that 89% of food-borne illness outbreaks
were linked to inadequate hand-washing by food handlers. Allwood, Jenkins, Paulus,
Johnson, and Hedberg (2004) found that only 52% of the persons in charge could
properly identify the correct procedure for hand-washing as defined in the food code, and
only 48% of food workers could demonstrate proper hand-washing. Clayton, Griffith,
Price, and Peters (2002) found that 64% of food workers perceived no risk of food-borne
illness being transmitted in their establishment. Some of the most commonly reported risk
factors that contribute to food-borne illnesses are poor personal hygiene; contamination
of potentially hazardous foods with pathogens; and failure to maintain proper
temperatures, such as leaving food at room temperatures for an extended period of time
and insufficient time/temperature control (Olsen et al., 2000).
In a study on chicken handling practices, Brown, Khargonekar, Bushnell, and the
EHS-Net Working Group (2013) discovered that only 43% of managers knew the final
cook temperature of chicken. Brown et al. found that 86% of kitchen managers did not
follow the FDA recommended guidelines to properly cool food. Identifying and
correcting risk factors associated with food-borne illness by managers and employees

who are trained in food safety may decrease violations and possibly reduce food-borne
illness outbreaks. However, a gap remains in the literature where several studies have
suggested that critical risk factors and employee behaviors may not be affected by food
safety training (Averett, Nazir, & Neuberger, 2011; Phillips et al., 2006; Reske, Jenkins,
Fernandes, VanAmber, & Hedberg, 2007).
Purpose of the Study
The purpose of this quantitative study was to examine (a) the relationship between
having a CFSM and the number of risk factors cited on restaurant inspections in Georgia,
(b) whether restaurant operation type (i.e., chain vs. independent restaurant) has an
impact of the number of risk factors cited on restaurant inspections, (c) the relationship
between having a CFSM and the restaurant food safety score identified on restaurant
inspections, and (d) whether restaurant operation type (i.e., chain vs. independent
restaurant) has an impact on the restaurant food safety score. The presence of a CFSM
and type of restaurant (chain or independent) were the independent variables, and the
number of risk factors cited during restaurant inspections and restaurant food safety score
were the dependent variables. Health inspections provide restaurant managers the
opportunity to be educated on food handling practices and help them identify and correct
unsafe food handling practices. Identifying risk factors and the corrective actions taken
by employees who have had food safety training may lead to a decrease in critical
violations; food safety programs might be better designed to assist operators in
understanding food safety laws and codes along with the importance of food safety
practice in restaurants.

Research Questions and Hypotheses
RQ1—Quantitative: What is the relationship between having a CFSM and the
number of risk factors (defined as poor personal hygiene, contamination with potentially
hazardous pathogens, failure to maintain proper temperature, and insufficient
time/temperature control) found or identified in restaurant food inspections?
H01: There is no association between having a CFSM and the number of risk
factors (defined as poor personal hygiene, contamination with potentially hazardous
pathogens, failure to maintain proper temperature, and insufficient time/temperature
control) found in restaurant food inspections.
HA1: There is an association between having a CFSM and the number of risk
factors (defined as poor personal hygiene, contamination with potentially hazardous
pathogens, failure to maintain proper temperature, and insufficient time/temperature
control) found in restaurant food inspections.
RQ2—Quantitative: Does the restaurant operation type (i.e., chain vs.
independently owned) have an impact on the number of risk factors (defined as poor
personal hygiene, contamination with potentially hazardous pathogens, failure to
maintain proper temperature, and insufficient time/temperature control) cited on
restaurant food inspections?
H02: There is no association between number of risk factors (defined as poor
personal hygiene, contamination with potentially hazardous pathogens, failure to
maintain proper temperature, and insufficient time/temperature control) cited on
restaurant food inspections and the restaurant operation type.

HA2: There is an association between the number of risk factors (defined as poor
personal hygiene, contamination with potentially hazardous pathogens, failure to
maintain proper temperature, and insufficient time/temperature control) cited on
restaurant food inspections and the restaurant operation type.
RQ3—Quantitative: What is the relationship between having a CFSM and the
restaurant food safety score identified on food safety inspections?
H03: There is no association between having a CFSM and the restaurant food
safety score identified on food safety inspections.
HA3: There is an association between having a CFSM and the restaurant food
safety score identified on food safety inspections.
RQ4—Quantitative: Does the restaurant operation type (i.e., chain vs.
independently owned) have an impact on the restaurant food safety score identified on
food safety inspections?
H04: There is no association between the restaurant food safety score identified on
food safety inspections and the restaurant operation type.
HA4: There is an association between the restaurant food safety score identified on
food safety inspections and the restaurant operation type.
Theoretical Base
The epidemiological triangle is a model (Merrill, 2012, pp. 8-9) that is commonly
used in public health. The model demonstrates the connection between an agent, a host,
and the environment. The agent could be biological, chemical, or physical. A disease is
caused by an agent; the host, which is usually a human or an animal, harbors the disease;
and the environment includes surroundings around the human or animal that allow for
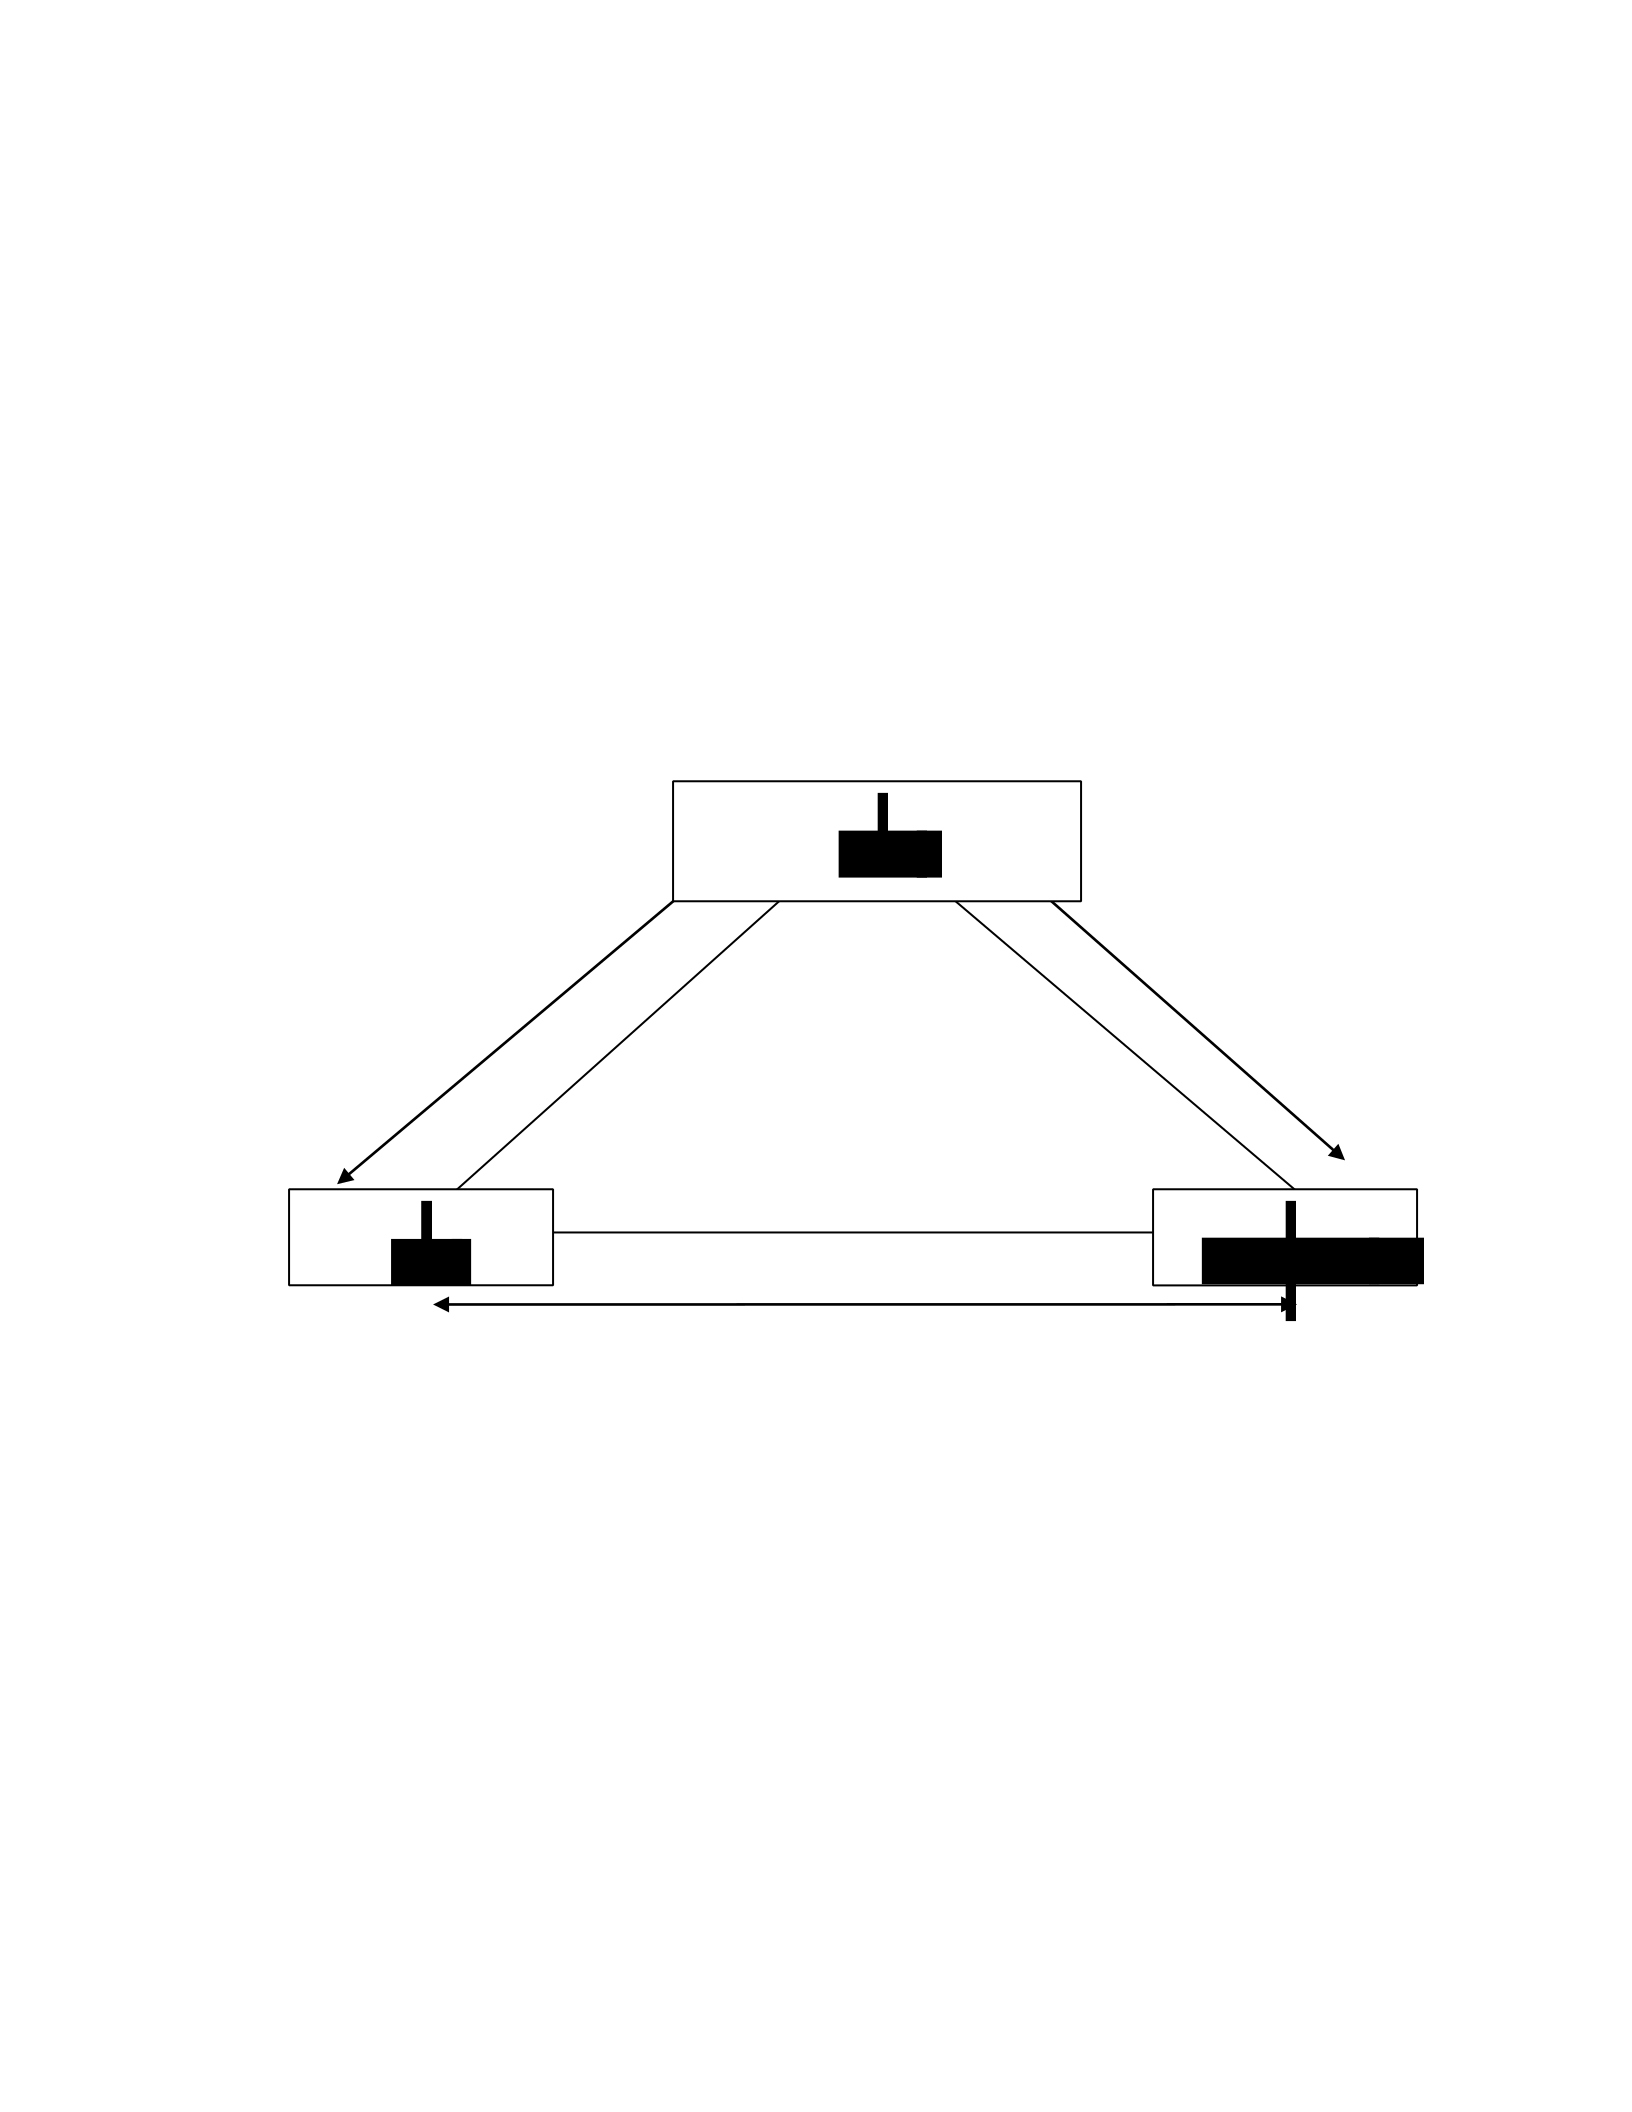
transmission of the disease (Merrill, 2012, pp. 8-9). For this research, the agent would be
biological (e.g., Salmonella), the host would be the customer, and the environment would
be the restaurant. The epidemiological triangle model was the most effective framework
for this study, because a CFSM has the ability to implement interventions for food safety
to break the chain of transmission of food-borne illness by identifying and correcting
unsafe food handling practices.
Epidemiological Triangle
Figure 1. The epidemiological triangle. From Introduction to Epidemiology (6th ed., pp. 8-
9), by R. M. Merrill, 2012, Burlington, MA: Jones & Bartlett Learning.
Nature of the Study
Using a quantitative comparative and associational non experimental research
methodology, 2013 restaurant food safety inspection data obtain from health departments
in Georgia were analyzed. This study used existing publically available secondary data,
and no new data were collected. The sample consisted of restaurants located in North,
Environment
Host
Agent

Central, and South Georgia health districts that were randomly selected, including Risk
Type 2 facilities and facilities receiving only routine inspections. Bars, institutions, and
schools were excluded. Critical violations were reviewed based upon the violations that
the FDA has designated as risk factors.
Data from health inspection forms were copied into SPSS for analysis.
Descriptive statistical analyses were performed. A two-tailed independent samples t test
was conducted to assess Research Hypotheses 1, 2, 3 and 4.
Operational Definitions
Certified food safety manager (CFSM): Owner or manager of a food service
establishment who has successfully completed and passed a professionally validated
CFSM examination that is accredited by the Conference for Food Protection or other
accrediting agency as conforming to national standards for organizations that certify
individuals (Georgia Department of Public Health, n.d.).
Critical items: Violations that to contribute to food contamination, illness, or
environmental health hazard and may create an imminent health hazard (Georgia Department
of Public Health, n.d.).
Food-borne illness: Commonly called food poisoning; refers to any illness
resulting from the consumption of contaminated food caused by pathogenic bacteria,
viruses, prions, or parasites (CDC, 2012).
Hazard Analysis Critical Control Point (HACCP): Based on seven principles that
identify significant biological, chemical, or physical hazards at specific points in a
product’s flow (ServSafe, 2013).

Person in charge: Individual present at a food service establishment who is responsible
for the operation at the time of inspection (Georgia Department of Public Health, n.d.).
Risk factors: Factors that contribute to food-borne illness outbreaks commonly
reported to the CDC: improper holding temperatures, improper cooking temperatures,
contaminated utensils and equipment, poor personal hygiene, and food from unsafe
sources (CDC, 2012; FDA, 2009a).
Risk Type 2 facilities: Establishments that are inspected two times per year that
cook and/or hold and reheat food that is prepared onsite (Georgia Department of Public
Health, n.d.).
Assumptions
Several assumptions were made for this study. I assumed that health inspectors did
correctly identify critical violations associated with risk factors that contribute to food-
borne illness. It was assumed that food handlers who do not practice food safety are likely
to continue to mishandle food if they are not knowledgeable about food safety practices.
It was also assumed that CFSMs are implementing the knowledge gained from food
safety certification class to reduce the behaviors that are associated with critical
violations.
Scope, Delimitations, and Limitations
The scope of this study included restaurants located in North, Central, and South
Georgia health districts—that is, the study was delimited to restaurants located in North,
Central, and South Georgia that were in operation in 2013. The study was delimited to
only Risk Type 2 facilities. Health inspectors’ documentation of critical violation is
subject to personal interpretation. Georgia food rules and regulations may not be

generalizable to other health jurisdictions, as food rules and regulations may vary by
state. The study was limited to 2013, and no attempt was made to extrapolate the results
of this study outside of the population sampled. Only critical violations from health
inspections were examined.
Significance of the Study
In the United States, a significant source of food-borne illness comes from food
prepared outside the home. Data from the CDC from 1998-2004 showed that 52% out of
9,040 food-borne illness outbreaks reported were related to food service establishments
(Jones & Angulo, 2006). A study conducted by Scharff (2012) estimated that food-borne
illness cost the United States $77.7 billion annually in health-related costs. A study
conducted by Green et al. (2005) revealed that unsafe food preparation practices are
common in food workers. Additionally, a study by the FDA (2009a) revealed that in
54.7% of full-service establishments and in 38.2% of fast food establishments, proper
holding and time/temperature control procedures were not followed correctly; and in
40.9% of full-service establishments and in 24.2% of fast food establishments, personal
hygiene practices were not followed correctly. Several factors have an impact on food
safety in food service establishments: (a) inspections conducted by local or state
inspectors, (b) knowledge of the FDA Food Code, and (c) proper training of managers
and food workers (Bryan, 2002; FDA, 2009a). Although food safety certification is not
mandated in the FDA Food Code, the code does recognize certification by an accredited
program in which the person in charge can effectively demonstrate knowledge on
foodborne illness preventive measures and apply HACCP principles (FDA, 2009b).

Proper training in food safety of managers and food workers is significant because
the costs associated with food-borne illness result in an estimated $7.7 to $23 billion
impact annually for consumers, the food industry, and the economy (Council for
Agricultural Science and Technology, 1995). Managers who have positive attitudes and
view food safety practices as important are more likely to promote food safety practices
among workers (Mortlock, Peters, & Griffith, 2000). Restaurants face many challenges in
trying to prevent food-borne illness outbreaks, such as employees not being adequately
trained in food handling and high turnover rates (Jones & Angulo, 2006). Therefore,
CFSMs play a significant role and have the essential duty to ensure that food workers are
properly trained in food safety practices that reduced the risk of food-borne illness (Cates
et al., 2009).
In the State of Georgia, from 1997-2002 there were 4,800 cases of food-borne
illness that were reported (Georgia Department of Human Resources, 2005). Salmonella
was the most common food-borne pathogen reported, making up 35% of food-borne
illness cases, followed by food-borne pathogens Giardia, Campylobacter, and Shigella
(Georgia Department of Human Resources, 2005). In 2008, there were 2,562 reported
cases of Salmonella outbreaks related to food-borne illness. There is also a higher
incidence of food-borne illness in the southern parts of Georgia (Georgia Department of
Public Health, 2008). Using the FDA Food Code as a reference, Georgia implemented
rules and regulations on food safety and developed inspection forms and scoring
standards. The state of Georgia mandates that all restaurants have at least one CFSM
(Georgia Department of Public Health, n.d.).

Even though establishments are in compliance by having a CFSM, the violations
cited on inspection reports show that employees are not being trained effectively
(Hammond, Brooks, Schlottmann, Johnson, & Johnson, 2005). With a CFSM, risk factors
that are known to cause food-borne illness should be decreased. Control measures should
be in place that prevent outbreaks or at least reduce the occurrence of food-borne illness
in all facilities (Cates et al., 2009). Analyzing inspection reports by examining the
violations gives a clear understanding of whether these control measures are working to
mitigate risk factors known to cause food-borne illness (Jones et al., 2004)). Results of
the study could be used to identify specific training needs for restaurant managers and
workers to maximize training efficiency.
More importantly, knowledge gained from this study could aid food intervention
programs in focusing on training food employees not only on food safety, but also on the
importance of how factors (e.g., time/temperature control, hand-washing) have an impact
on the practices of food handling (Green et al., 2005; Green & Selman, 2005). Using
inspections from restaurants to educate workers on food handling practices may decrease
critical violations, thus minimizing food-borne illness. In addition, programs could be
developed and implemented that contribute to a better understanding of effective food
safety handling practices of restaurants (Jones et al., 2004). DeBess et al. (2009)
suggested that knowledge gained from food safety training is not being used in
restaurants and that more effective education is needed.
Summary
The purpose of Chapter 1 was accomplished as stated in the introduction by
establishing the framework of the study. An introduction of the subject matter and a

statement of the problem were provided, and the purpose of the study was described.
Research questions/hypotheses were presented, along with a justification of the need for
the study. In addition, basic assumptions, delimitations, limitations, and definitions of
terms were discussed. Chapter 2 follows with a comprehensive review of the literature
related to the study topic and methodology.

Chapter 2: Literature Review
Introduction
Food safety programs such as Servsafe teach managers food safety concepts,
increasing their knowledge of food safety practices and ways to identify risk factors
associated with food-borne illness (Howells, 2008; ServSafe, 2013; York, 2009). Despite
such programs, several studies have reported that risk factors and unsafe food handling
practices by employees may not be affected by food safety training (Averett et al., 2011;
Phillips et al., 2006; Reske et al., 2007). Cotterchio, Gunn, Coffill, Tormey, & and Barry
(1998) suggested that manager training and certification in food safety have been
effective in increasing sanitary conditions and inspection scores of food service
establishments. The purpose of this study was to examine the relationship between having
a CFSM and the number of risk factors cited on restaurant inspections. I also analyzed the
association of restaurant operation type (chain vs. independent restaurant) on risk factors
cited on restaurant inspections. Next, I examined the relationship between having a
CFSM and the food safety score. Finally, I examined the association of restaurant
operation type (i.e., chain vs. independent restaurant) on food safety score.
This chapter is a review of the extant literature related to this research. In it, I
summarize evidence of an association of food safety programs and food handling. In the
first section, I discuss the causes of food-borne illness in restaurants and how inspections
provide a guideline as to what areas of food safety need improvements to reduce the
occurrence of food-borne illness. I review the evidence related to the role of food safety
and training and present an overview of managers being trained and certified in food
safety. Studies that address food safety barriers are also presented. Following this, I

present studies related to the methodology that were used for the study. Finally, I
highlight the gaps in the current literature on food safety.
Literature Search Strategy
In the literature search, I reviewed articles from 1989 to 2013 that addressed
critical and noncritical risk factors, food safety education, food safety practices,
effectiveness of food safety training, and impact of having a CFSM. A range of online
databases and search engines were used to conduct the study, such as Academic Search
Premier, Walden University library, Proquest, PubMed, and Google Scholar. Key search
terms were food safety, food safety education, certified food safety managers, food safety
practices, ServSafe, restaurants food-borne illness outbreaks, critical violations, and food
safety training. Additional research was conducted using citations of articles in the
literature. Further research was conducted to identify and download more articles related
to food safety using the key terms.
Theoretical Framework
I used the epidemiological triangle model as the theoretical framework. The model
consists of three corners: agent, environment, and host. The agent causes the disease, the
host harbors the disease, and the environment allows for transmission of the disease. This
model is commonly used in public health to study infectious diseases and how they are
spread (Merill, 2012). A disease is transmitted when the agent leaves the source through
either indirect or direct contact and enters the susceptible host; this is referred to as the
chain of infection (CDC, 2012). For this study, I applied the epidemiological triangle in a
restaurant setting; the agent is the microorganism, the customer is the host, and the
environment is the restaurant.

In a restaurant, a food-borne illness outbreak occurs when two or more persons
experience a similar illness after ingesting the same food (CDC, 2012). Food can become
contaminated from a biological, chemical, or physical (ServSafe, 2013). CDC (2013)
reported that from 1998 to 2008, 68% of cases of food-borne illness were associated with
restaurants or delis, and 7% involved catering and banquet facilities. Food handlers can
contaminate food in many ways, such as person-to-person contact, not properly sanitizing
food-contact surfaces after working with raw food items before working with ready-toeat
food, touching dirty food-contact surfaces, working while ill, and improper cooking
(ServSafe, 2013). In a case study conducted by Kassenborg et al. (2004), individuals
infected with Escherichia coli O157:H7 were linked to consuming ground beef at a
sitdown restaurant. Roderiques et al. (2001) found that consumption of chicken prepared
at a restaurant was associated with cases of Campylobacter jejuni. In a study on chicken
handling practices, Brown et al. (2013) found that more than 50% of managers did not
use a thermometer to check the final cook temperature of chicken and that one-third did
not properly wash and rinse food-contact surfaces before sanitizing. A study conducted on
ill food workers by Summer et al. (2011) revealed that 20% of respondents reported
working while ill with symptoms such as vomiting and diarrhea on at least one shift and
that 12% reported working while ill with the same symptoms on two shifts or more.
Simple mistakes and risky food handling practices in restaurants by managers and food
service workers are what contributes to the transmission of pathogens that cause
foodborne illness.
Having managers who are properly trained and certified and food workers who are
properly trained is important to ensure that food is being handled safely (Jones & Angulo,

2006). Ultimately, CFSMs have the responsibility to implement food safety training
programs to break the chain of transmission by identifying and correcting unsafe food
practices. Breaking the chain of transmission disrupts the link among the agent, host, and
environment, which in turn prevents the spread of food-borne illness (CDC,
2012).
Inspections and Food Safety
Food-Borne Illness
A food-borne illness outbreak occurs when two or more people eat food that has
been contaminated by a disease-causing agent. Food-borne illness in the United States
remains a significant problem for public health (Mead et al., 1999), and it is well known
that many food-borne illness outbreaks that are reported originate in food service
establishments (Olsen et al., 2000). Guzewich and Ross (1999) and Olsen et al. (2000)
suggested that poor personal hygiene of food workers is a contributing factor to
foodborne illness outbreaks. With restaurants being the location commonly identified for
food-borne illnesses, it is critical that employees and managers understand the causes of
food-borne illness and ways to prevent food-borne illness.
To gain a better understanding of the risks associated with restaurants and
foodborne illness, a network of environmental health specialists referred to as EHS-Net
was established. EHS-Net conducts food safety research and surveillance in restaurants,
identifying how and why food-borne illness outbreaks occur and translating the
knowledge into preventive practices (Hedberg et al., 2006). Important information on
food safety policies and practices has been found by EHS-Net in conducting these
environmental assessment studies. Heberg et al. (2006) found that food service

establishments that had a CKM were less likely to have an outbreak and had fewer
outbreaks associated with norovirus and bare hand contact. Although temperature and
time control is critical in limiting the growth of food-borne bacteria, Bogard, Fuller,
Radke, Selman, and Smith (2013) found that 65% of restaurants did not use a
thermometer to check the temperature of ground beef when receiving a shipment.
Likewise, Coleman et al. (2013) found that only 7.5% of managers reported ever refusing
leafy greens due to the greens being received above the proper temperature; however, it
was observed that half of the shipment was received above the proper temperature of
41°F.
It is well known that cross-contamination and improper cooking temperatures
contribute to the burden of food-borne illness; several studies have been conducted and
have observed these two risk factors. Brown et al. (2013) conducted a study on
restaurants that handle raw chicken and discovered that 40% of managers typically did
not designate separate cutting boards for raw meat and ready-to-eat food. In a similar
study on ground beef handling among restaurants, Bogard et al. (2013) revealed that in
62% of restaurants, no hand-washing was observed when switching from handling raw
ground beef to ready-to-eat food. Also, only 46% of managers in the Brown et al. study
used a thermometer to determine whether the chicken reached the final cooking
temperature of 165°F, and only 12% of managers reported in the Bogard et al. study that
they used a thermometer to check to determine whether hamburgers had a final cooking
temperature of 160°F. These unsafe food practices allow food-borne pathogens time to
grow and contaminate food.

The risk that is of greatest concern for food-borne illness transmission involves
employees working while ill. Carpenter et al. (2013) interviewed food service workers
and discovered that 20% reported working while having symptoms such as vomiting and
diarrhea. From 2001 through 2008 in the United States, food service workers were linked
to food-borne illness outbreaks of norovirus (Hall et al., 2012). The FDA (2009b) has
designated specific symptoms associated with food-borne illness, which include
vomiting, diarrhea, jaundice, sore throat accompanied by a fever, and open wounds. The
FDA indicated that five food-borne illnesses are commonly transmitted through food—
Salmonella, Shigella, Norovirus, Shiga-toxin producing E. coli, and Hepatitis A—and
must be reported by an employee to a manager or person in charge. Clearly, it is
important that managers and employees understand the causes of food-borne illness and
appreciate the need for not working while ill, good hygienic practices, and practicing
food safety to prevent food-borne illness outbreaks. In addition, employees should be
trained in order to understand and gain knowledge of food safety practices and should be
observed by a manager who is certified in food safety.
In the United States, policies, rules, and regulations are established by regulatory
agencies to help control food safety hazards. Health inspections are conducted to evaluate
sanitary conditions to assess the risk of food-borne illness and observed food handling
practices of employees (Almanza et al., 2003; Anding, Boleman, & Thompson, 2007;
Cates et al., 2009; Jenkins et al., 2004). Health inspectors document critical and
noncritical violations that are associated with food-borne illness outbreaks and suggest
corrective actions (FDA, 2009b). Protecting the safety of the food is a responsibility that
managers and employees share. Knowing how bacteria can cause food-borne illness,

keeping everything clean, and storing and preparing food safely help to cut down on
contamination.
Health Inspections’ Role in Food Safety and Food-Borne Illness
Health inspections are conducted in restaurants to prevent food-borne illness by
ensuring that food is handled correctly and prepared safely. However, health inspections
alone have not been effective in reducing critical violations due to unsafe food handling
practices (Cruz et al., 2001; Jones et al., 2004; Newbold et al., 2008; Phillips et al., 2006).
In an earlier study, Irwin et al. (1989) analyzed the association between routine
inspections and food-borne illness in restaurants and found a significant association
between inspections and food-borne illness from restaurants. Recreating the study by
Irwin et al. 1989, Cruz et al. (2001) tested the association between food-borne illness and
violations cited during routine inspections using a random sample of 127 restaurants that
were divided into those that had outbreaks (n = 51) and those with no outbreaks (n = 76).
However, there were no statistically significant differences between the two groups, and
no critical violations had been cited among 45% of the case restaurants prior to an
outbreak. Results indicated that restaurant inspections alone do not effectively predict
outbreaks, but that food safety training and a HACCP plan are needed in the prevention
of food-borne illness.
Critical violations pose substantial health hazards and are likely to contribute to
food-borne illness. Statewide inspection data from restaurants in Tennessee from
19932000 were examined by Jones et al. (2004). A total of 167,575 restaurant inspections
were examined to determine whether inspection scores could predict food-borne illness.
Researchers reported that there was no significant difference between mean scores of

restaurants with reported outbreaks and mean scores for those with no reported outbreaks.
Violations most commonly cited during routine inspections among restaurants with
reported outbreaks were the same ones cited among restaurants that were not involved in
outbreaks. However, Cruz et al. (2001) found that case restaurants, when compared to the
controls, were three times more likely to be cited for vermin and had larger seating
capacities; both variables are related to outbreaks. Jones et al. reported that before an
outbreak was reported, the mean score for the restaurant’s last inspection was 81.2% and
was 81.6% for the previous inspection was, whereas restaurants with no reported
outbreak had mean scores from 80.2% to 83.8%. However in the Cruz et al. study, case
restaurants’ scores were less to be the most favorable (70%), while the control group had
a rating of 80%. One limitation to the Jones et al. study was limited data on outbreaks in
Tennessee, which suggested that scores alone are not a direct reflection of a restaurant in
the prediction of food-borne illness. In both studies, violations most commonly cited
during routine inspections improper heating and cooling, improper cooking, holding, and
storage. More education and food safety training is needed in restaurants, along with the
appropriate regulatory action such as inspection follow ups in order to prevent the
occurrence of food-borne illness.
Scores alone are not a direct reflection on a restaurant in the prediction of
foodborne illness. Just because a restaurant scores 90 or above, one should not assume
that there were no critical violations cited that might pose a threat; likewise, a restaurant
with a score of < 80 may have several violations but no critical violations that pose a risk
for food-borne illness. In order to prevent food-borne illness, there are various additional
factors such as education, training, or a HACCP plan that need to be established. In

addition, researchers in the previous studies implied that other factors such as policies and
standardization of inspectors have an influence the inspection process of restaurants in
preventing food-borne illness. Health inspections of restaurants play a role in food safety
but alone are not enough in preventing food-borne illness. Inspections in general give a
snapshot showing what areas of an establishment need improvement.
Impact of Health Inspections
The objective of food safety inspections is the protection of the public from
foodborne illness. This objective is best met by conducting inspections documenting
critical and noncritical food safety violations and their corrective actions. Several studies
have examined the impact health inspections have on critical risk factors (Allwood, Lee,
&
Borden, 1999; Phillips et al., 2006; Simon et al. 2005; Reske et al., 2007). Phillips et al.
(2006) collected and analyzed random samples of food service inspections to determine
the rates of critical and recurrent violations and whether inspections had an impact in
decreasing unsafe food practices in medium- and high-risk establishments. Researchers
divided data into national chains, regional chains, and local chains and found that the rate
of recurrent violations was 50.9% for national chains, 55.6% for regional chains, and
51.6% for local restaurants. There were no critical violations observed in 8% to 10% of
establishments in 1996-2000 (Phillips et al., 2006), which implies that some
establishments practice food safety. Using inspection scores that are publicly posted,
Simon et al. (2005) conducted a study in Los Angeles County that assessed the impact of
the grading system on hospitalizations related to food-borne illness. Researchers found a
13.1% decrease of food-borne illness-related hospitalizations associated with the

implementation of grade cards. Both studies showed that inspections contain useful
information and can serve as a tool in food safety. Before the implementation of the
grading system, food-borne hospitalizations increased substantially year to year, followed
by an 18.6% decline after the first year of implementation in 1998, a 4.8% decline in
1999, and a 5.4% decline in 2000 (Simon et al., 2005). Based on the results from these
studies, it may be concluded that establishments that practice food safety and enforce
penalties for being in non compliance with food safety practices decrease violations
related to food-borne illness. In addition, there were several other factors that played a
role, such as training of inspectors and training and education of restaurant managers and
workers.
A food safety inspection is a written document that highlights unsafe food
handling and poor sanitary conditions of an establishment. Reske et al. (2007) examined
whether announced inspections are beneficial in improving restaurant inspections and
food safety. The authors reviewed a total of 1,314 inspections from June 2001 to August
2003, which were divided into categories based on inspection type: announced and
unannounced. The researchers found that restaurants with announced inspections had the
lowest number of violations cited, while whereas restaurants with unannounced
inspections had the highest number of violations cited (Reske et al., 2007). Allwood, Lee,
and Borden (1999) sought to determine whether inspection scores and the occurrence of
critical violations cited changed due to the impact of inspection frequency in full-service
facilities, small-scale restaurants, snack bars, and delicatessens; they discovered that
restaurants that were inspected frequently had better sanitary ratings. In addition,
Allwood et al. (1999) compared violations observed in 1987 and 1988 and found that

during the 2 years, there was an increase of food temperature violations, with a small
increase of violations related to hand-washing and to cleaning and sanitizing food-contact
surfaces. In both studies, critical violations that were cited the most frequently included
those related to holding temperatures of food, pest activity, hygiene practices, and
personnel.
In Reske et al. (2007), the most commonly violations associated with food safety
were cited more frequently in restaurants that received an unannounced inspection before
an announced inspection. There were two critical violations: a) person in charge,
demonstrates knowledge, and performs duties and b) prevention of food contamination,
that significantly decrease in restaurants that received an unannounced inspection
following an announced inspection. This coincides with Hedberg et al. (2006) study that
highlights cross contamination is a contributing factor to food-borne illness and having a
person in charge who demonstrates knowledge reduces food-borne illness. When foods
are improperly handled, this becomes a contributing factor in public health problems
(Wells & Butterfield, 1999). Resket et al. (2007) and Allwood et al. (1999) studies
demonstrated announced inspections and increasing inspection frequency could help
operators identify and handle issues related to food safety and help restaurants improve
their performance with decreasing violations. Education is the key and plays a major role
in helping restaurant manager effectively identify critical food safety issues. More
importantly, restaurants that have on-going inspections could significantly reduce
violations associated with food-borne illness.
The results of the Phillips et al. (2006) and Reske et al. (2007) studies suggested
inspections alone were not effective at minimizing violations. However, they are helpful

at identifying areas that pose a risk to food safety. As seen in the studies by Simon et al.
(2005) and Phillips et al. education plays a vital role and is needed for there to be a
significant change in compliance. Restaurant inspections are conducted to serve and
protect the public as well as the workers. An inspection serves as a tool that allows
managers and workers to have ongoing education in regards to food safety.
Food Safety Education and Training
The Importance of Food Safety Education
Food safety training allows food workers to gain knowledge on food safety and
help them engage in proper food safety practices. Onyeneho and Hedberg (2013)
conducted face to face interviews with managers and head cooks of hotel restaurants,
school cafeterias, fast food restaurants, and bacukaterias (e.g. food kiosks, roadside food
sellers) in the capital city of Nigeria. Researchers identified what areas managers and
head cooks are lacking in food safety knowledge and what areas in the restaurant need
hygiene and food safety improvements. Results revealed 38% of managers and head
cooks had correct knowledge regarding ideal refrigerator temperature while 36% had no
knowledge at all about refrigerator temperature. Ninety two percent reported cleaning and
sanitizing equipment and food contact surfaces, whereas 37% engaged in cross
contamination (Onyeneho & Hedberg, 2013). Several cases of food poisoning have been
reported due to yam flour consumption in Nigeria that was linked to employees
inadequately using chemicals (Adedoyin, Ojuawo, Adesiyun, Mark, & Anigilaje, 2008;
Adeleke, 2009). In another incident, acute gastrointestinal symptoms were reported that
resulted in 60 cases of patients and 3 deaths that were associated with consumption of
food at a burial ceremony (Fatiregun, Oyebade, & Oladokun, 2010).These findings

provide insight on food safety practices in restaurants, demonstrating there is a great need
for education among managers and food service workers and in the prevention of
foodborne illness and the possible hazards of food supply and storage.
Dundes and Swann (2008) conducted a case study using exploratory data from
experiences of a food service worker who was employed at 3 different fast food
restaurants and a cafeteria style facility. Inadequate training on food safety, or no training
received, time constraints, lack of resources and or managers not overseeing if their
employees are in compliance with food safety procedures such as hand-washing,
checking temperatures, and glove use were the main reasons for unsafe food practices.
Clayton et al. (2002) revealed employees who are trained sometimes deviate from
practicing food safety when under pressure due to time or lack of resources. These studies
prove there is an even greater need overseeing management of restaurants and for
managers to oversee if their employees are in compliance with food safety procedures.
While employers should not overwhelm employees with food safety information, it is
imperative they understand how not being in compliance with food safety rules can lead
to food-borne illness (Cotterchio et al., 1998). Therefore, it is important for managers to
ensure that employees understand the rules and regulations of food safety and the impact
it has on public health. Holding managers accountable for employees being in non
compliance and increasing emphasis on food safety education could help minimize risks
associated with food-borne illness.
Education is the key and plays a major role in helping restaurant managers
effectively identify critical food safety issues. A study conducted by Averett et al. (2011)
measured the effect of a food handler training program by comparing rates of noncritical

and critical violations of restaurants before and after implementation of a food handler
training program (FHT). Data was obtained from the Kansas City, Missouri Health
Department (KCMO-HD) on all routine health inspections before implementation
(20012004) and after (2005-2007). Before and after implementation of the FHT program,
total violations related to food handling were significantly less compared to control
violations. After implementation of the FHT program, overall violations related to food
handling and critical violation rates were reduced. Food handling violations decreased by
12.2%, whereas control violations decreased by 29.0%; both showing a statistically
significant decrease. For restaurants that were in operation and inspected during the entire
study, total violations related to food handling decreased by 20.2% while control
violations decreased by 32.8%; both showed a statistically significant decrease of 4.9%
and 24.7%
(Averett et al., 2011). Data from an earlier study by Fielding et al. (2001) using the same
FHT program suggested the program did have an impact on increasing compliance of
food safety in establishments and inspection scores. Worsfold and Griffith (2003)
compared food safety and hygiene training for staff in retail, caterers, and personal care
homes. Between May 2001 and July 2002, researchers surveyed 66 businesses that
handled raw meat and ready to eat (RTE) food in South Wales. Findings from Worsfold
and Griffith suggested majority of the managers assumed good food hygiene behavior is
common sense, held high standards with regard to hygiene training, and believe after
attending hygiene training staff attitudes and behaviors improved. Overall, the results
from the studies provide evidence that if businesses provide their staff with appropriate

food safety training this will help their staff understand, change their behaviors, and
attitudes towards food safety.
In addition, Averett et al. (2011) also conducted a separate analysis on
establishments who stayed in business and were inspected during the entire time of the
study (2001-2007) and found critical violations rates related to food handling were
significantly higher for restaurants that were in operation and inspected during the entire
study before and after implementation of the FHT program than control violations rates.
Violations related to food handling decreased by 13.1% and control violations decreased
by 47.7%; both showing a statistically significant decrease (Averett et al., 2011). In
Worsfold and Griffith (2003), researchers found more than 77% of the businesses
provided personal hygiene and health as topics in initial training; personal care homes
and caterers provided more hygiene awareness than butchers. Butchers had more than
70% of managers trained compared to caterers with 45% and personal care homes with
22%. Butchers also provided HACCP training to twice as many staff than caterers or
personal care homes and had nearly 48% of one or more staff who could be the person in
charge (PIC) (Worsfold & Griffith, 2003). Onyeneho and Hedbergh (2013) study supports
the notation that managers with food safety training were more knowledgeable in food
safety than those without food safety training. In general, if food safety training
standards among senior staff are recognize at high levels, there will be a greater
commitment to food safety among operational staff. Unsatisfactory of food safety training
systems of businesses are mostly due to lack of appropriate training of senior staff. The
data provided suggested the goal of food safety training is not just to increase the food
worker knowledge in food safety but also increase their behavior in food safety. A food

safety program should consider an active learning if possible, this could stimulate food
workers thinking skills and improved their retention of food safety knowledge, multiple
teaching methods, evaluations of outcomes, and qualitative evaluations could be used.
Green and Selman (2005) collected data on food workers’ and managers’ beliefs
on safe food practices using focus groups. Seven practices related to food safety were
discussed with food workers which included: hand-washing, cross contamination, gloves
used properly, proper cooking time and temperatures, hot and cold holding, proper
cooling time and temperature, and proper reheating. Improper implementation of these
seven food practices in restaurants has been linked to food-borne illness (Bryan, 1988;
FDA, 2009). Findings from both English and Spanish speaking workers and managers
identified factors that impacted their ability to practice food safety such as sink
accessibility, improper glove use, time and pressure when checking cooling, cooking, and
holding temperature. Participants however, did report safe food practices (e.g.
handwashing after working with raw meat, separate work spaces for raw meat and
vegetables (Green & Selman, 2005). Food workers in Kendall, Melcher, and Pauls (2000)
and Clayton et al. (2002) studies identified many of the same factors that impacted their
ability to practice food safety. Bryan (1988) indicated most food-borne illness outbreaks
are linked to improper handling of food by food service workers. Among both food
workers and managers, eight factors were discussed with two or more food safety
practices: time pressure, equipment, manager/co-worker emphasis, worker characteristics,
negative consequences, education and training, restaurant procedures, gloves and
sanitizers. However, the two factors that were consistently identified among the
participants were time pressure and structural environments.

Green and Selman (2005) suggested management has an influence on many of
those factors and plays a vital role in ensuring food workers practice food safety. The
authors’ findings also support FDAs argument that active managerial control is important
to ensure food safety practices are being implemented (FDA, 2001). Food safety
programs in the future should make sure there is considerable focus on management,
active food managerial control, and food safety education. In addition, food safety
education must address other factors that have an impact on food workers ability to
practice food safety.
Food workers can transmit pathogens to food through hand contact; therefore,
proper hand-washing is essential in order to minimize the transmission of pathogens. In a
study, Green et al. (2006) gathered observational data on food workers hand-washing
practices and examined the relationship between glove use and hand-washing.
Researchers found food workers attempted hand-washing in only 32% of work activities
and only use appropriated hand-washing in only 27% of work activities. In 24% of work
activities, gloves were worn where hand-washing should have taken place; and in 36% of
work activities gloves were removed at which hand-washing should have occurred.
Workers used soap in 28% of work activities and in 31% of work activities workers dried
their hands with paper or cloth towels. Rates revealed in only 28% of work activities,
workers used soap and in 31% of work activities workers dried their hands with paper or
cloth towels; indicating soap is usually omitting by food workers in hand-washing.
Surprisingly, in only 23% of work activities workers washed their hands appropriately
after handling raw meat. (Green et al, 2006). In a survey conducted by Onyeneho and

Hedberg (2013), 70%of food workers washed their hands before preparing food, while
20% did most of the time and 10% some of the time; concluding hand-washing is not
practiced by all food workers.
In a report by FDA (2004), 73% of food workers were observed engaging in
improper hand-washing at full service establishments. In a study conducted by Clayton
and Griffith (2004), researchers found only 9% of food workers adequately wash their
hands. In a review by Guzewich and Ross (1999), 89% of food-borne outbreaks were
caused by employees transmitting pathogens to food through hand contact. Findings
suggest food workers hand-washing practices needs improvements. Also, results revealed
a pattern of hand-washing and glove use among workers that if: (a) if workers are
wearing gloves where hand-washing should take place, they are less likely to wash their
hands, and (b) workers who are going to be wearing gloves during work activities are less
likely to wash their hands before work than workers without glove activities. However,
the observations provides data on how frequently and in what situations food workers
engage in hand-washing activities.
Research has suggested food workers do not engage in proper hand-washing and
glove use in food service establishments as often as they should. Gloves can be effective
in minimizing the transfer of pathogens between hands and food if worn properly
(Michaels et al., 2004; Montville, Chen, & Schaffner, 2001). Green et al. (2007)
identified factors related to food worker hand hygiene practices in food service
establishments which included: 196 (61%) independently owned, 121 (38%)
franchise/chains, and 4 (1%) establishments had missing ownership. Workers were
observed engaging in a total of 2,195 work activities which including handling dirty

equipment, food preparation, preparing raw animal product, putting on gloves before
handling food, eating, drinking, coughing, or sneezing. In 27% of work activities,
workers appropriately washed their hands while gloves were worn in 28% of work
activities (Green et al., 2007). In two observational studies, Clayton et al. (2002) and
Green et al. (2006) discovered a third of food workers do not wash their hands as
frequently as they should, and Guzewich and Ross (1999) provided evidence that gloves
may enable food workers to wash hands less frequently. Green et al. also discovered
restaurants where workers received food safety training; appropriate hand-washing was
more likely to occur. Researchers found ownership of the restaurant were related to glove
use as well, in which workers of chain restaurants were more likely to wear gloves than
workers of independently owned restaurants. In food preparation areas where gloves were
more accessible, gloves were also worn more frequently. Results indicated appropriate
hand-washing as well as glove use varies among food workers activity. It is also an
indication improvement is needed in hygiene practices among food workers. In addition,
findings specifies that are several factors that relate to hand-washing practices but
programs must also address additional factors such as activity type, number and location
of hand sinks, availability of supplies, food safety training, and restaurant ownership.
Health inspectors play an important role and have the responsibility to ensure food
service operators are complying with food safety codes. Also, research suggest there are
numerous factors related to operation type that could impact the inspection score. Lee,
Nelson, and Almanza (2012) examined restaurant scores and the probability of violations
found differ by inspector and operation types. The inspections included were routine
inspections that were classified as full-service, limited-service, fast food, taverns, and

schools. Results of their study suggested significant differences between operation type
and inspection score based on the inspector. In a study conducted by Seiver and Hatfield
(2000), researchers found operations that had simple menus tended to score higher on
inspections than those operations with more complex menus; the results also suggested
the size of the facility may have an effect on the inspection score. Olsen et al. (2000)
indicated restaurants, delicatessens, and cafeterias are associated with more foodborne
illness outbreaks. Frash, Almanza, and Stahura (2003) found full-service chain restaurants
have statistically more violations than independent full service restaurants. In a study
conducted by Medeiros and Wilcox (2006), inspectors were interviewed to investigate
potential bias or the amount of influence their decision had on food service inspection.
Researchers found their decisions were personal and bias, both having an influence on
their decisions during inspections. To prevent bias, Peacock (2000) suggest there should
be a different inspector at each inspection of a facility. Based on the findings, these
studies provide evidence inspectors and operation types does have an influence on
violations cited. Of the ten most frequently cited violations, five were considered risk
factors as reported by the CDC (CDC, 2012). Establishing what areas of deficiency a
restaurant has could be used to identify training needs for inspectors and managers. Using
the most frequently cited violations, along with the probability that an inspector will find
those violations, will aid in implementing training programs that could maximize
efficiency.
Evaluation of Food Safety and Training
Food handlers play an important role in contributing or preventing food-borne
illness, therefore education and training in food safety are crucial. DeBess et al. (2009)

evaluated food handlers (FHs) food safety knowledge and practices in Oregon using a
survey based on Oregon’s Food Handler Certification (FHC) program. Overall, 68% was
the average score achieved by FHs on the survey. A score of 70% on Oregon FHC test is
considered passing. The scores collected showed significant differences for managers and
FHs with some college education with an average score of 74% and 73% to those who
worked on the line with an average score of 67%; and FHs with no college education with
a score of 64%. FHs that held a food handlers card FHC scored 69% and FHs that did not
hold a FHC scored 63%. Participants answered 90% of questions correctly regarding food
contamination and sanitation; while questions related to cooking temperature, cooling,
storage, thawing, hand-washing, hygiene, and refrigeration received the lowest scores
(DeBess et al., 2009). Hislop and Shaw (2009) conducted a study in Alberta, Canada
evaluating certified and non certified food handlers knowledge on food safety, using a
questionnaire developed by Environmental Public Health Service (EPHS). Researchers
found there was a significant difference observed in passing scores both in the 50th and
70th percentile among certified food handlers than non certified food handlers. Non
certified food handlers that had 10 or more years of experience and less than 1 year in the
food service industry failure rates were higher than those of certified food handlers. Data
provided demonstrates FHs limited level of food safety knowledge.
Food handlers’ lack of food safety knowledge may result in the transmission of foodborne
illness. To ensure safe food handling in restaurants, more education is needed to delineate
the most effective means of conducting safe food handling among FHs.
DeBess et al. (2009) emphasized educational programs need to be structured to
improve FHs food safety knowledge of food-borne illness. Equal access to food safety

training should be necessary for all food handlers (Hislop & Shaw, 2009). This can
contribute to a better understanding of food safety concepts that help minimizes the risks
of food-borne illness (FDA, 2009c). To ensure safe food handling in restaurants, more
education is needed to delineate the most effective means of conducting safe food
handling among food handlers.
One way food handlers obtain food safety knowledge is through food safety
training. Park, Kwak, and Chang (2010) evaluated a food safety training program to test
its effectiveness at improving food safety knowledge and practices of food handlers.
Food handlers’ knowledge of food safety and practices were evaluated before and after
the food safety training. Scores from the food safety knowledge test revealed there was
not a significant difference between the control group and the intervention group before
training. In addition, there was not a significant difference in the control group pre and
post test scores. However, after receiving training, the intervention group post-test
knowledge on sanitation increased to a total of 66.6 points; which was 49.3 points before
training (Park et al., 2010). Previous studies have tested how effective hygiene education
is among food handlers and discovered education alone does not improve attitudes and
hygiene practices of food handlers (Chang, Lee, & Kwak, 2003; Walker, Pritchard, &
Forsythe, 2003). Tokuc, Ekuklu, Berberoglu, Bilge, and Dedeler (2009) found
inconsistencies exist among food workers hygiene attitudes and hygiene practices.
However, Park et al. study showed no increase in food safety knowledge in the group that
received training compared to the group without training. On the other hand, as far as
food safety practices, no significant difference was observed in the control group.

Surprisingly, even though food safety knowledge increased in the intervention group after
training, there were no significant changes in food safety practices after training in the
intervention group.
Areas where knowledge increase significantly after training included: food-borne
illness, employee health, proper cold holding, glove use, optimal temperature for bacteria
growth, proper cooking temperatures, cross-contamination, washing fruits and vegetables,
equipment and facility management. There were also significant increases of knowledge
in food handling and serving but improvement is needed in the personal hygiene section.
It is concluded if employees are provided with continuing training that address key
element of food safety, food handlers could possible improved food safety practices such
as hand-washing, clean and sanitation of equipment, cross-contamination.
Restaurants are ideal locations for food-borne illness outbreaks. Hedberg et al.
(2006) conducted a systematic environmental evaluation of outbreak and non outbreak
restaurants from June 2002 to 2003 comparing food handling practices and restaurants
characteristics. A total of 22 restaurants with outbreaks and 347 non outbreak restaurants
evaluations were conducted. Researchers found norovirus was the most common
identified food-borne pathogen, accounting for 45% of outbreaks. Salmonella and
Clostridium perfringens together accounted for another 28% of outbreaks. In addition, the
most commonly contributing factors identified in outbreaks were: food handled by an
infected person (65%) and bare-hand contact with ready to eat food (35%) (Hedberg et
al., 2006). Research conducted by FoodNet discovered the risk of food-borne illness
increases when eating food prepared outside the home (Jones & Angulo, 2006). In a
previous study Olsen et al. (2000) found 45% of food-borne illness outbreaks reported to

the CDC between 1993 and 1997 originated in restaurants. In Hedberg et al., the main
difference between outbreak and non outbreak restaurants was the presence of a CKM. In
outbreak restaurants 32% had a CKM, whereas, in non outbreak restaurants 71% had a
CKM. Bare-hand contact was identified as a contributing factor in 47% of outbreaks in
establishments without a CKM. Also, there were fewer norovirus and Clostridium
perfringens outbreaks in establishment where a CKM was present (Hedberg et al., 2006).
Cates et al. (2009) study suggest the presence of a CKM is effective in dealing with most
types of critical violations such as personnel, food source and handling, ware-washing,
and physical facilities. However, the presence of a CKM was not effective in handling
critical violations related temperature and time control. Temperature and time control of
food is among one of the five risk factors related to food-borne illness (FDA, 2009c).A
study by Green et al. (2005) revealed food handlers commonly engage in unsafe food
preparation and found 53% of respondents did not properly check food temperatures.
Findings suggested having a CKM presence reduced risks associated with food-borne
illness outbreaks; this was identified as a major difference between outbreak and non
outbreak restaurants. It is imperative to properly store, cook, cool, and hold potentially
hazardous food items at the proper temperatures in order to destroy food-borne
pathogens. CKMs perhaps are more liable than non certified kitchen managers to
effectively trained and communicate food safety practices to food workers.
Manager Training and Certification
Effectiveness of Manager Training and Certification
In retail establishments food handlers are associated with many food-borne illness
outbreaks; therefore, it is essential managers as well as food workers are thoroughly

trained in food safety practices. According NRA (2013), training is the most powerful
weapon to combat food handling problems that are seen in majority of food service
establishments. Lynch, Elledge, Griffth, and Boatright (2003) conducted a study in
Oklahoma to evaluate managers’ knowledge on basic food safety principles. Surveys
were administered to restaurant managers that contain thirteen questions related to food
safety. Overall, results indicated knowledge in food safety was high among respondents
87.2%, but there were some significant deficiencies of knowledge in certain areas of food
safety. Higher scores (92.8% average score) were achieved from respondents who
received both training from health department and corporate training, whereas the
respondents with no formal training in food safety had the lowest scores averaging
79.5%. Respondents who received health department training performed better than those
who had received corporate training by approximately 10 points. Also, respondents who
held a food service operator certificate significantly outscored respondents who were not
certified (Lynch et al., 2003). Mathis, Sizto, Halzewood, and Cocksedge (1995)
conducted a study and found inspections scores improved after managers and food
workers completed food safety education. However, Mathis et al. (1994) found no
significant association between food safety training and violations cited on inspections.
In the Lynch et al. (2003) study, researchers found respondents with no formal
training performed the poorest on survey questions and could not properly identify
handwashing techniques, proper holding temperatures, and food storage. In addition,
respondents who received only cooperate training had no understanding of properly
separating and storing raw meats and they were uncertain of the temperature danger zone
for bacteria (Lynch et al., 2003). The Lynch et al. study indicated managers with food

safety training were more knowledgeable in food safety than those who received no
formal training, and managers who were certified food safety operators had better
knowledge of food safety than noncertified food safety operators. Training in food safety
from the health department appeared to be more effective than corporate training.
Managers who received health department training demonstrated more knowledge in food
safety compared to managers who received corporate training. For the most part,
managers had limited knowledge on proper holding temperatures and the danger zone for
bacterial growth. Given that inadequate cooking and holding temperatures have been
identified as risk factors for food-borne illness, it is extremely important that managers
are educated in food safety and should have corrected, memorized information of these
factors.
Restaurant managers are introduced to training and certification programs to
educate them in safe food handling practices. Cotterchio et al. (1998) evaluated the
effectiveness of a training and certification program for restaurant managers in increasing
inspection scores. Researchers analyzed routine inspections from 1989 to 1992 for three
groups of restaurants: a mandatory group, a voluntary group, and a control group. The
overall mean for inspections scores were 73 at baseline, 81 at Post 1, and 84 at Post 2;
showing a significant difference from baseline to Post 2. The mandatory group scored a
66 at baseline which was significantly lower than the control group baseline score of 77,
whereas the voluntary group baseline score was 74. Following one year after
implementing the training and certification program, the mandatory group had an increase
of 14.7 points on their inspection score and the voluntary group had an increase of 7.5
points (Cotterchio et al., 1998). Both mandatory and voluntary groups maintained their

improvements on their inspection scores at the two year follow up, while the control
group inspection score did not have a significant change over time. Kassa et al. (2010)
examine food safety violations of facilities to see if having trained and certified food
managers had an effect on violations. Kassa et al. found food service facilities that had
personnel who were certified had considerably fewer critical violations compared to
facilities without certified personnel. However, food service establishments that had
certified personnel had more noncritical violations than facilities with uncertified
personnel.
The results of Cotterchio et al. (1998) showed that the training and certification
program for managers had a positive effect on food-handling knowledge of the managers
that participated in the class. Critical violations found at the restaurants decreased
significantly after one year of the manager training and certification program and were
even sustained after two years. Since the control group inspection scores did not change
significantly but there was improvement in scores from the mandatory group and
voluntary group, suggest the manager training and certification program had an impact.
Data supports that a manager training and certification program may be an effective way
to sustain improvements in sanitary conditions of food service establishments at the same
time reducing the burden of food-borne illness.
To ensure food service establishments are in compliance with food safety
regulations, many health departments regulate food safety inspections and mandate
training and certification of food personnel. In a study using inspection reports from
Central Florida, Murphy, DiPietro, Kock, and Lee (2011) investigated the association
between mandatory training and certification in food safety and inspection results among

chain and independent restaurants. Researchers found the total number of violations cited
was 66; 46 critical and 33 non-critical. The risk factor with the most number of violations
cited was protection from contamination with a mean average of 2.01, which indicates
restaurants had at two violations in this category on average. Next was time and
temperature control with an average of 1.42, followed by total approved source with 1.03
and certification with 1.02. Violations that fell within toxic items had the least number
with an average of .40. For noncritical violations as well as total violations, there was not
a significant difference observed between restaurant types (Murphy et al., 2011). Kassa et
al. (2010) examined if trained and certified managers had an effect on violations in
highrisk operations and found majority of critical violations cited fell within the category
of time and temperature control and cross contamination. Next in line were violations due
to lack of cleaning equipment and utensils. Majority of noncritical violations were due to
equipment not operation and properly maintain, followed by violations due to non-food
contact surfaces being clean and unapproved equipment. Although certification in Kassa
et al. study did not have an impact on the number of violations cited, however, data did
revealed certification plays an important role. In Murphy et al. there was not a significant
difference in the number of total violations among chain or independent restaurants,
suggesting perhaps mandatory certification programs mitigated these effects.
The overall purpose of having certified personnel is improvement in food safety,
thus minimizing the occurrence of food-borne illness. Certified personnel in the Kassa et
al. (2010) study received training that focused primarily on theoretical concepts of food
safety with little or no hands on approach. In a study conducted by Lillquist, McCabe,
and Church (2005), food handlers who received both lecture and hands on training test

scores were statistically better than food handlers who received only lecture. By health
departments establishing and implementing a mandatory certification and training for all
food service workers, possibly indicates that mandatory certification and training is
essential for all food service operations to reduce risk factors that can lead to food-borne
illness outbreaks. In addition, mandatory certification of personnel could lead to
improvement of scores on food safety inspections.
Impact of a Certified Food Safety Manager
Research suggested certification of managers in food safety helps improve
sanitary conditions of restaurants and food safety practices of food handlers. Cates et al.
(2009) conducted a study analyzing health inspections during 2005 and 2006 to study the
effect between CKMs and sanitary conditions of restaurants. Inspections reports were
collected from three categories of food service establishments: restaurants that served
liquor, restaurants without liquor, and taverns that sell food. Out of 4,461 food service
establishments 79% had at least one critical violation during the 2 year period. The total
number of critical violations for all establishments was 13,444 during the 2 year period.
Average number of critical violations for restaurants that served liquor was 3.9,
restaurants without liquor 2.7, and taverns that sold food 2.4. A CKM was on hand for at
least one inspection at 29% of restaurants that served liquor, 30% of restaurants without
liquor, and 7% of taverns that prepared food. Out of all the establishments, taverns had
the least number of critical violations as well as a CKM present probably because of the
limited amount of food preparation (Cates et al., 2009). Hedberg et al. (2006) found
foodborne illness is less likely to occur if a CKM is presence. In Cates et al. study,
establishments who had a CKM present was less likely to have a critical violation in all

inspection categories. Also, establishments with a CKM present were more successful at
handling critical violations dealing with personnel, food source and handling,
warewashing facilities, and physical facilities. However, establishments with a CKM
present were not effective in controlling critical violations related to temperature and time
control, water, plumbing and waste and the same goes for establishments without a CKM
present. Results revealed CKMs maybe effective at improving food safety practices
among food handlers. These findings imply that CKMs who have completed proper food
safety training and certification are knowledgeable in risk factors and safe food handling
practices and possibly more likely to enforce and follow food safety practice to minimize
food-borne illness.
Mandatory certification is an effective tool that maybe used to ensure managers
are knowledgeable in safe food safety practices. To evaluate whether certification and
training had an impact, Ravel-Nelson and Smith (1999) surveyed certified and
noncertified food service workers about knowledge gained in food safety from training. A
questionnaire was developed consisting of 13 questions related to food safety which
included hand-washing, equipment and utensil sanitization, cross-contamination,
HACCP, thawing methods, and processing. Results revealed those who were certified in
food safety had knowledge on the minimum cooking temperature of ground beef;
however, certified and noncertified individuals were not knowledgeable on the minimum
cooking temperature of chicken. Individuals who were certified in food safety performed
better than noncertified food handlers. Almanza and Nesmith (2004) suggested risk
factors such as time and temperature control, personal hygiene, and cross contamination

could be better controlled with better training and found there are 17 states/jurisdictions
that currently have rules and regulations that require a certified food safety manager.
Having a nationally food safety standard for the testing of certified managers would help
eliminate inconsistencies between state food safety rules and regulations. More emphasis
should be placed on minimum cooking temperatures of potentially hazardous foods as
well as the principles of HACCP. Further education and training is needed to encourage
safe food handling practices.
Food Safety Education Barriers
Research conducted on food service workers perceptions of barriers to practice
food safety has been limited. Using focus groups, Howells et al. (2008) conducted a study
to identify perceived barriers of three food safety practices: time and temperature control,
personal hygiene, and cross contamination. Researchers divided focus groups into
participants that received food safety training and participants that did not receive food
safety training. Participants without training identified a total of 43 barriers for the three
food safety practices. Of the 43 barriers, trained participants identified: 15 barriers for
cleaning and sanitizing, 14 barriers for hand-washing and 14 barriers for using a
thermometer. In contrast, a total of 47 barriers were identified in the focus groups that
received food safety training: 21 barriers for cleaning and sanitizing, 12 for handwashing,
and 14 for using a thermometer (Howell et al., 2008).The most commonly reported
barriers by both groups were time constraints, inadequate training, and insufficient
resources. The barriers mentioned by participants did not address food safety knowledge,
thus training that focuses only on food safety knowledge may not help food service
workers in overcoming barriers. Howells et al. results could aid managers in developing

and implementing programs that address barriers not covered in food safety training,
which might improve food safety practices. Managers have a responsibility to ensure
employees are trained regularly, employees’ food safety practices are being monitored,
and sufficient supplies are available. Educating employees on the risks of not properly
handling food could improve attitudes towards food safety.
A 2-year longitudinal study was conducted by York et al. (2009) whom
investigated the effectiveness of a food safety training program using the Theory of
Planned Behavior to target employees’ perceived barriers to food safety practices.
Researchers targeted hand-washing, thermometer usage, and food-contact and non-food
contact work handling surfaces and found knowledge of hand-washing statistically
increased after training, whereas knowledge of thermometer us-age and handling of food
and non-food contact surfaces did not (York et al., 2009). Overall, behavioral compliance
for all three food safety practices were significantly higher at post-intervention than at
baseline and post-training. Pilling, Brannon, Shanklin, Howells, and Roberts (2008) used
the Theory of Planned Behavior to identify beliefs held by food service workers to
improve the same three food safety practices as York et al. Researchers discovered
attitudes were the main significant variable for performing the three food safety practices.
For each food safety practice, participants with lower intentions had less positive
attitudes. Overall, for all three food safety practices, employees with lower intentions
were less likely to perform the task to practice food safety. However, for thermometer
usage and sanitization, those with lower intentions thought not being properly trained
made it difficult to complete the tasks (Pilling et al., 2008). Results suggested food safety
training improved knowledge, but training alone did not improve behaviors. In order to

improve employees’ attitudes towards food safety, managers should encourage employees
that practicing food safety reduces food-borne illness and reduces the spread of bacteria,
which in turn keep customers happy. Managers should consider implementing an
intervention along with training to improve food safety knowledge and practices of
employees.
There are numerous barriers to food safety education. Some of the barriers include
improper training, inadequate supplies, and time constraints. Howell et al. (2008), Pillling
et al. (2008), and York et al. (2009) provided evidence that employees want to engage in
safe food handling practices after food safety training. Those researchers also suggested
implementing an intervention could target those barriers. Combining food safety training
with an intervention could aid employees in overcoming barriers to food safety and be in
compliance with rules and regulations of food safety (Howell et al.,
2008, Pilling et al., 2008, & York et al., 2009).
Studies Related to Methodology
The author has proposed a quantitative comparative and associational
nonexperimental design that will use food safety inspections to examine the relationship
between CFSMs and risk factors cited on food safety inspections, does operation type
have an impact on risk factors cited on food safety inspections, the relationship between
having a CFSM and the restaurant food safety score, and does the restaurant operation
type have an impact on the restaurant food safety score. Several researchers have used
food safety inspection reports to examine food handling practices and determine if
foodborne illness outbreaks can be predicted. In Settle, King County, Irwin (1989)
analyzed the association between routine food safety inspections and food-borne illness

outbreaks in restaurants. Cruz et al. (2001) in their study of an assessment of restaurants
in Miami-
Dade County Florida used food safety inspections tested the association between
violations cited on inspection reports and food-borne illness outbreaks. Jones et al. (2004)
examined restaurants inspection reports in Tennessee to determine if scores received
could predict food-borne illness outbreaks. Random samples of food safety inspection
reports were used to decide if inspections had an impact of food handling practices in
restaurants from Oklahoma City-County Health Department and Oklahoma State
Department of Health (Phillips et al., 2006). Reske et al. (2007) examined inspection
reports from restaurants that received an announced inspection to determine if food
handling practices were better compared. All of these studies demonstrate that a
comparative and associational non-experimental design using food safety health
inspections is a possible method to examine food handling practices and possibly predict
food-borne illness outbreaks in restaurants.
Researchers have also used food safety inspection reports to examine the
effectiveness of training and certification on sanitary conditions of restaurants. Averett et
al. (2011) evaluated routine health inspections to determine if food safety training had an
impact on violations cited on inspection reports. Cotterchio et al. (1998) analyzed routine
inspection reports to see if a training and certification program for managers had an effect
on inspection scores. Food inspection reports were used to determine if a certified and
trained food safety manager had an impact on violations (Kassa et al., 2010). Murphy et
al. (2011) used inspection reports from Florida to examine the relationship between
training and certification of managers in food safety and violations cited on inspection

reports in chain and independent restaurants. Cates et al. (2009) utilize health inspections
to study the effect a certified manager had on a restaurant sanitary condition. Food safety
inspections has been utilized to collect data on food handling practices and determine if
food-borne illness outbreaks can be predicted, as well as examine if certification and
training has an effect on sanitary conditions in a variety of studies in food service
establishments.
Information Gaps
The literature has been inconclusive on the effectiveness of food safety programs
in regards to critical violations and employee food safety practices (Averett et al., 2011;
Phillips et al., 2006; Reske et al., 2007). With many food service workers lacking
adequate knowledge in food safety, many states are now slowly beginning to require
mandatory certification of managers as a way to demonstrate knowledge in food safety
(Almanza & NeSmith, 2004). Cotterchio et al. (1998) suggested training and certification
in food safety has been effective on sanitary conditions and inspection scores of food
service establishments. However, training has limited long-term effect on some critical
risk factors. In a systematic review conducted by Campbell et al. (1998), researchers
found in some studies inspection scores did improve after training and certification,
however, in some studies no improvement was observed after training and certification.
Without a doubt, it is imperative to recognize if training and certification of managers
reduces risks associated with food-borne illness. If certification is not effective at
controlling and reducing risks that lead to food-borne illness, then there is no need for
certification.

Several studies have been conducted showing food safety practices are not being
followed. In Roberts and Sneed (2003) study restaurant managers in Iowa were surveyed,
and researchers found 43.2% had no procedures for cleaning and sanitizing equipment,
24% had no hand-washing policy, and 46% had no procedures for checking temperatures of
food received. A report by the FDA (2009a) found the most out-of-compliance food safety
practices that occur in full service restaurants include holding potentially hazardous food
below 41 °F 77.8%, inadequate cooling of potentially hazardous food 77.3%, and date-
marking potentially hazardous foods 74.2%. In fast food restaurants, researchers found the
most out-of-compliance food safety practices were date-marking of commercially
processed foods 57.6%, holding potentially hazardous food below 41 °F 56.5%, and date-
marking potentially hazardous foods 40.7%. With many people eating at restaurants on a
regular basis, it is important for managers and food service workers to practice food safety
to prevent food-borne illness.
Summary
In the United States, restaurants are inspected regularly by health departments to
make certain food safety codes are being met. Review of the literature demonstrates when
health inspections of restaurants are conducted for food safety practices, an evaluation of
food handlers’ knowledge of food safety practices maybe indicated (Green et al., 2005,
Mathis et al., 1994; Mathis et al., 1995). DeBess et al. (2009) suggested there is a need
for food safety training and certification and re-certification maybe necessary to keep up
with current food technology and food safety practices. The FDA (2009b) reported 48 of
the 56 states and territories have used the Food Code as their foundation to adopt food
safety codes. However, Jones et al. (2004) found after reviewing statewide inspection

data from Tennessee there were inconsistencies between inspectors and food safety
standards even though the same rules and regulations, forms, and procedures were used in
inspecting restaurants. Establishing effective food safety rules and regulations may
possibly reduce risk factors associated with food-borne illness in restaurants. Restaurant
managers have the ultimate responsibility to ensure safety of their patrons by adhering to
food safety rules and regulations.
Training of all personnel involved in food safety is vital to reduce the burden of
food-borne illness. Education was found to play an important role in changing the
knowledge and behaviors of food workers (Phillips et al. 2006; Reske et al., 2007; Simon
et al., 2005) but other factors also play a role in practicing food safety. Clayton et al.
(2002), Green and Selman (2005), and Kendall et al. (2000) studies identified similar
factors that impact food handlers’ ability to practice food safety. These factors were time
pressure, limited resources, accessibility, equipment, training, and management. Pragel et
al. (2007) also found management, training and education affected food handling
practices among food workers. Cates et al. (2009) and Ravel-Nelson and Smith (1999)
found that certification has an impact on food handling practices. Having managers
certified in food safety appears to play a vital role in the prevention of food-borne illness
and food handling practices. This study should contribute to the literature by providing
data on how effective CFSMs are on the number of risk factors cited on restaurant
inspections in Georgia. Also, whether restaurant operation type (chain vs. independent)
has an impact on the number of risk factors cited on restaurant inspections, the
relationship between having a CFSM and the restaurant food safety score, and whether
restaurant operation type has an impact on a restaurant’s food safety score.

Chapter 3 describes the research design of the study, data collection, and analysis.
The purpose of this chapter was to summarize the methods and procedures used to
collect, tabulate, and analyze the research data. This chapter addresses the methodology
employed in conducting the research project, including materials, collection of samples,
and statistical analysis.

Chapter 3: Research Method
Many states are now turning toward mandatory certification of managers in food
safety (Almanza & NeSmith, 2004). It has been suggested that CFSMs play a significant
role in reducing risk factors and employee behaviors associated with food-borne illness
(Cates et al., 2002). The purpose of this study was to examine the relationship between
having a CFSM and the number of risk factors cited on inspection reports, whether
operation type (chain vs. independent) has an impact on the number of risk factors, the
relationship between having a CFSM and the restaurant food safety score, and whether
restaurant operation type has an impact on a restaurant’s food safety score.
This chapter contains the research design and methodology used to examine the
relationship between CFSMs and risk factors cited on food safety inspections, whether
operation type has an impact on risk factors cited on food safety inspections, the
relationship between having a CFSM and the restaurant food safety score, and restaurant
operation type has an impact on a restaurant’s food safety score. A description of the
setting, sample size, and sampling method of inspections is presented. Instrumentation
and materials are also discussed, along with statistical analyses and statistical tests. This
chapter concludes with a summary.
Research Design
A cross-sectional design was used for this study. The design included several
archival variables assessed in restaurants in Georgia. The study’s main independent
variables were the presence of a CFSM and type of restaurant (major chain or
independent). The study’s main dependent variables were the number of risk factors cited
during restaurant inspections and the restaurant score.

There are many advantages and disadvantages of the cross-sectional non
experimental design. First, the archival nature of the variables gives the researcher an
opportunity to evaluate hypotheses without introducing bias because the assessment has
already concluded. Such designs are helpful for assessing theoretical differences and
relationships to guide and build theory and practice. An often-overlooked benefit of any
non experimental design is that it offers researchers the opportunity to investigate
processes that would be unethical or impossible to investigate with a more sophisticated
experimental approach. This is of particular concern for researchers in the social and
epidemiological sciences.
The main disadvantage of using any non experimental design is that the researcher
cannot imply causality. That is, statistical significance within this design cannot imply
cause-and-effect relationships. Other disadvantages include the great number of
potentially confounding or extraneous variables that can impact the dependent variable
but are not considered in the study. However, confounding variables are always a
concern in a non experimental design, regardless of the researcher’s experience,
attempts at accurate measurement, and the vigor of procedures.
Methodology
Setting and Sample
The setting for this study was the state of Georgia. The sample included health
inspections from restaurants located in North, Central, and South Georgia Health
Districts. North Georgia Health District is composed of six counties, Central Georgia is
composed of 13 counties, and South Health District is composed of 10 counties. Only
routine health inspections and Risk Type 2 facilities were included in the study. Risk Type

2 facilities are associated with food handling practices that may lead to a foodborne
illness outbreak. A restaurant that had 10 or more units was categorized as a chain, and
any restaurant that was not part of a chain was considered independent. Bars, institutions,
and schools were excluded from this study.
Sample Size Justification: A Priori Power Analysis
There are several ways to determine the sample size for a quantitative study. A
common strategy is to determine the number of participants required to reach a specified
level of statistical power given fixed parameters. A priori power analysis was used to this
end. An a priori power analysis was conducted to determine the number of restaurants
required to detect a medium effect (d = .50) with power = .80 given the following testing
parameters: a two-tailed independent samples t test conducted at = .05. The analysis
indicated that a sample size of 128 would detect a medium effect given these parameters.
The power analysis was conducted with the software G*Power 3.1.4 (Faul, Erdfelder,
Buchner, & Lang, 2009).
Instrumentation and Materials
The data for this study were accessed through each health district’s website.
Therefore, the data obtained were public data, and no instrument tool was used for this
study. Each district website contained a link to view restaurant scores and violations
cited. Critical and noncritical violations are recorded by health inspectors during routine
inspections on food service inspection reports. The report has three sections: the first
section contains information about the restaurant, such as name of establishment, date,
risk type, and purpose of inspection. The second section contains citations based on

Georgia Food Rules and Regulations; depending on their potential to cause an imminent
health hazard, violations are categorized as food-borne illness risk factors, public health
interventions, or good retail practices. Violations cited under food-borne illness risk
factors and public health interventions have a greater potential to cause a food-borne
illness. The third section contains an area to record temperatures, to document violations,
and to note corrective actions. Once the inspection is finished, the CFSM or PIC signs the
report and receives a copy; an additional copy is filed at the local health department.
Data Collection and Analysis
To obtain health inspection reports, each health district website was accessed to
query restaurants. Restaurants were sorted by risk type and violations. The study’s main
independent variables were the presence of a CFSM and type of restaurant (chain or
independent), and the study’s main dependent variables were the number of risk factors
cited and the restaurant score. The data were entered into SPSS. All statistical tests were
conducted at α = .05. The following is a review of the data analysis procedures that were
used to assess each research hypothesis.
RQ1: Is there a statistically significant difference between restaurants that have a
CFSM and the number of risk factors (defined as poor personal hygiene, contamination
with potentially hazardous pathogens, failure to maintain proper temperature, and
insufficient time/temperature control) found or identified in restaurant food inspections?
H01: There is not a statistically significant difference between restaurants that have
a CFSM and the number of risk factors (defined as poor personal hygiene, contamination
with potentially hazardous pathogens, failure to maintain proper temperature, and
insufficient time/temperature control) found or identified in restaurant food inspections.

HA1: There is a statistically significant difference between restaurants that have a
CFSM and the number of risk factors (defined as poor personal hygiene, contamination
with potentially hazardous pathogens, failure to maintain proper temperature, and
insufficient time/temperature control) found or identified in restaurant food inspections.
RQ2: Is there a statistically significant difference between restaurant operation
type (i.e., chain vs. independently owned) in the number of risk factors (defined as poor
personal hygiene, contamination with potentially hazardous pathogens, failure to
maintain proper temperature, and insufficient time/temperature control) cited on
restaurant food inspections?
H02: There is not a statistically significant difference between restaurant operation
type (i.e., chain vs. independently owned) in the number of risk factors (defined as poor
personal hygiene, contamination with potentially hazardous pathogens, failure to
maintain proper temperature, and insufficient time/temperature control) cited on
restaurant food inspections.
HA2: There is a statistically significant difference between restaurant operation
type (i.e., chain vs. independently owned) in the number of risk factors (defined as poor
personal hygiene, contamination with potentially hazardous pathogens, failure to
maintain proper temperature, and insufficient time/temperature control) cited on
restaurant food inspections.
RQs 1 & 2: A two-tailed independent samples t-test (Howell, 2010; Moore, 2000)
was conducted to assess Research Hypotheses 1 and 2. A separate t-test was conducted
for each hypothesis. The number of risk factors cited during restaurant inspections were
the dependent variables, and the presence of a CFSM (yes vs. no) was the

betweensubjects independent variable for Hypothesis 1. The number of risk factors cited
during restaurant inspections were the dependent variables, and the type of restaurant
(chain vs.
independent) was the between-subjects variable for Hypothesis 2.
The following analytical procedures were followed for each t test. The
restaurants’ dependent variable scores were standardized by group, and the resulting
zscores were used to identify outliers in the data. A restaurant was considered an outlier
when the standardized score was greater than 3. If the sample size was greater than 50
for a group, normality was assumed given the central limit theorem. Histograms were
displayed for each group to assess the normality assumption if a group had less than 50
restaurants. In addition, the Kolmogorov-Smirnov test was used if the histograms did not
provide a conclusive test of normality. If a serious violation of the normality assumption
occurred, the non parametric equivalent of the t test (i.e., Mann-Whitney test) was used.
Levene’s test was used to assess the homogeneity of variances assumption. The degrees
of freedom were adjusted in cases of a significant Levene’s test to compensate for
heterogeneity of variances. A t-test table and descriptive statistics are also displayed for
each test.
RQ3: Is there a statistically significant difference between having a CFSM and the
restaurant food safety score identified on food safety inspections?
H03: There is not be a statistically significant difference between having a CFSM
and the restaurant food safety score identified on food safety inspections.
HA3: There is a statistically significant difference between having a CFSM and the
restaurant food safety score identified on food safety inspections .

RQ4: Is there a statistically significant difference between restaurant operation
type (i.e., chain vs. independently owned) in the restaurant food safety score identified on
food safety inspections?
H02: There is not a statistically significant difference between restaurant operation
type (i.e., chain vs. independently owned) in the restaurant food safety score identified on
restaurant inspections.
HA2: There is a statistically significant difference between restaurant operation
type (i.e., chain vs. independently owned) in the restaurant food safety score identified on
restaurant inspections.
RQ 3 & 4: A two-tailed independent samples t-test (Howell, 2010; Moore, 2000)
was conducted to assess Research Hypotheses 3 and 4. A separate t-test was conducted
for each hypothesis. The restaurant food safety score identified on restaurant inspections
was the dependent variable, and the presence of a CFSM (yes vs. no) was the
betweensubjects independent variable for Hypothesis 3. The restaurant food safety score
identified on restaurant inspections was the dependent variable, and the type of restaurant
(chain vs. independent) was the between-subjects variable for Hypothesis 4.
The following analytical procedures were followed for each t test. The
restaurants’ dependent variable scores were standardized by group, and the resulting
zscores were used to identify outliers in the data. A restaurant was considered an outlier
when the standardized score was greater than 3. If the sample size was greater than 50
for a group, normality was assumed given the central limit theorem. Histograms were
displayed for each group to assess the normality assumption if a group had less than 50
restaurants. In addition, the Kolmogorov-Smirnov test was used if the histograms did not

provide a conclusive test of normality. If a serious violation of the normality assumption
occurred, the non parametric equivalent of the t test (i.e., Mann-Whitney test) was used.
Levene’s test was used to assess the homogeneity of variances assumption. The degrees
of freedom were adjusted in cases of a significant Levene’s test to compensate for
heterogeneity of variances. A t-test table and descriptive statistics are also displayed for
each test.
Protection of Human Participants
The data collected and analyzed was from secondary publically existing data. A
random number was assigned to each facility to protect the restaurant’s identity. No
information on human participants were collected or used in this study. Institutional
Review Board (IRB) approval number 09-12-14-0174737.
Reliability and Validity
Validity concerns how well a procedure measures what it is intended to measure,
whereas a tool that is considered reliable if it can produce the same results repeatedly.
Because the data were collected by health inspectors and not by me, it was not feasible to
directly measure the reliability and validity of the data used in the study. However, one
can generalize that reliability is based upon what the health inspector documents on the
food inspection report form. In the State of Georgia, all health inspectors go through
standardization. In standardization, the health inspector must (a) complete and pass an
examination that is accredited by the Conference for Food Protection and (b) demonstrate
knowledge and understanding of Georgia Food Service Rules and Regulations Chapter
290-5-14, food-borne illness risk factors, public health interventions, HACCP principles,
and communication skills necessary to conduct food service inspections.

Summary
The purpose of Chapter 3 was to discuss the research design, methodology, and
procedures used to collect, tabulate, and analyze the research data. This chapter addressed
the methodology employed in conducting the research project, including materials,
collection of samples, statistical analysis, reliability, and validity. A quantitative research
design was used to examine the possible relationship between a CFSM and the number of
risk factors cited on inspection reports, whether operation type (chain vs. independent)
has an impact on the number of risk factors, the relationship between a CFSM and the
restaurant food safety score, and whether operation type (chain vs. independent) has an
impact on the restaurant food safety score. The following chapter provides the results of
the analysis.
Chapter 4: Results
Restaurants are the precursor of many reported food-borne illnesses (Olsen et al.,
2000). Two factors that have been implicated in these illnesses are inadequate safety and
hygiene procedures among employees (Alllwood et al., 2004) and a lack of understanding
by restaurant managers (who may or may not have CFSM designations) of the risk of
food-borne illness being transmitted (Clayton et al., 2002). Therefore, the purpose of this
quantitative study was to examine (a) the relationship between having a CFSM
designation and the number of risk factors cited on restaurant inspections in Georgia, (b)
differences between chain vs. independent restaurant in terms of the number of risk
factors cited on restaurant inspections, (c) the relationship between having a CFSM
designation and food safety scores identified on restaurant inspections, and (d)

differences between chain and independent restaurants in terms of food safety score
identified on restaurant inspections. In this chapter, I provide the results, including
descriptive statistical analyses and the results for each of the research questions.
The research questions and associated null and alternative hypotheses for this
study were the following:
RQ1—Quantitative: What is the relationship between having a CFSM and the
number of risk factors found or identified in restaurant food inspections?
H01: There is an association between having a CFSM and the number of risk
factors found in restaurant food inspections.
HA1: There is no association between having a CFSM and the number of risk
factors found in restaurant food inspections.
RQ2—Quantitative: Does the restaurant operation type (i.e., chain vs.
independently owned) have an impact in the number of risk factors cited on restaurant
food inspections?
H02: There is no association between number of risk factors cited on restaurant
food inspections and the restaurant operation type.
HA2: There is an association between the number of risk factors cited on restaurant
food inspections and the restaurant operation type.
RQ3—Quantitative: What is the relationship between having a CFSM and the
restaurant food safety score identified on food safety inspections?
H03: There is no association between having a CFSM and the restaurant food
safety score identified on food safety inspections.

HA3: There is an association between having a CFSM and the restaurant food
safety score identified on food safety inspections.
RQ4—Quantitative: Does the restaurant operation type (i.e., chain vs.
independently owned) have an impact on the restaurant food safety score identified on
food safety inspections?
H04: There is no association between the restaurant food safety score identified on
food safety inspections and the restaurant operation type.
HA4: There is an association between the restaurant food safety score identified on
food safety inspections and the restaurant operation type.
Data Collection
Data from 2013 obtained from North, Central, and South Georgia health districts
were used to assess the research questions. The key variables in this study were the
presence of a CFSM, type of restaurant (major chain or independent), the number of risk
factors, and the restaurant score. The presence of a CFSM and type of restaurant (major
chain or independent) were the independent variables, and the number of risk factors
cited during restaurant inspections and the restaurant score were the dependent variables.
This study was limited to routine inspections of Risk Type 2 facilities. Risk Type 2
facilities are associated with food handling practices that may lead to a food-borne illness
outbreak. If a restaurant had 10 or more units, it was labeled as chain, and any restaurant
not labeled as chain was considered independent.
Descriptive Statistics
Data for a total of 1,547 restaurants were available for this study, including 647
(41.8%) from central Georgia, 375 (24.2%) from southern Georgia, and 525 (33.9%)

from northern Georgia. Descriptive statistics for the independent variables are shown in
Table 1. The majority of the restaurants (88.5%) had a CFSM, and most (55.6%) were
independent restaurants.
Table 1
Descriptive Statistics for Independent Variables (N = 1,547)
Variable n %
Presence of a CFSM
No
178
11.5
Yes
1369
88.5
Type of restaurant
Independent
860
55.6
Chain
687
44.4
Table 2 contains descriptive statistics for the two dependent variables. The
number of risk factors identified in the restaurant inspections ranged from 0 to 5 with a
mean of 1.18 (SD = .67). The food safety scores ranged from 41 to 97 with a mean of
85.65 (SD = 7.60).
Table 2
Descriptive Statistics for Dependent Variables (N = 1,547)
Variable
Minimum
Maximum
M
SD
Number of risk factors
0
5
1.18
.67

Food safety scores
41
97
85.65
7.60
Inferential Statistics
Preliminary Analyses
Two preliminary analyses were performed. First, the distributions of scores on the
two dependent variables were examined for outliers. Standardized scores (z scores) were
created and examined to determine how many scores were greater than 3 standard
deviations above or below the mean. For the number of risk factors, there were only 12
outliers (0.7%) with z scores ranging from 4.19 to 5.68. For the food safety scores, there
were 32 outliers (2.1%) with z scores ranging from -5.88 to -3.11. However, due to the
large sample sizes in this study, it was assumed that the central limit theorem would
ensure that the sampling distribution of the mean for the null hypothesis tests would be
normal. Specifically, sample sizes for all groups were greater than 50, and therefore
normality was assumed based on the central limit theorem as described in Chapter 3.
Second, Levene’s test was used to assess the homogeneity of variances
assumption required for the independent-samples t tests. As described below, four
independent-samples t tests were performed. In the analyses of differences in risk factors
between restaurants that had a CFSM and restaurants that did not have a CFSM, Levene’s
test was statistically significant, F = 28.30, p < .001. In the comparison of major
restaurant chains and independent restaurants in terms of the number of risk factors,
Levene’s test was statistically significant, F = 24.50, p < .001. In the analyses of
differences in food safety scores between restaurants that have a CFSM and restaurants
that do not have a CFSM, Levene’s test was statistically significant, F = 34.02, p < .001.

Finally, in the comparison of major restaurant chains and independent restaurants in terms
of food safety scores, Levene’s test was statistically significant, F = 28.93, p < .001.
Thus, in all four cases, the assumption of the homogeneity of variances was not met, and
therefore the degrees of freedom adjustment to the independent-sample t test results are
reported below.
Research Question 1
The first research question of this study were: Is there a statistically significant
difference between restaurants that have a CFSM and restaurants that do not have a
CFSM on the number of risk factors cited during restaurant inspections? The null and
alternative hypotheses for this study was:
H01: There is not a statistically significant difference between restaurants that have
a CFSM and restaurants that do not have a CFSM in the number of risk factors cited
during restaurant inspections.
HA1: There is a statistically significant difference between restaurants that have a
CFSM and restaurants that do not have a CFSM in the number of risk factors cited during
restaurant inspections.
In order to test the null hypothesis, a two-tailed independent sample t test was
performed comparing restaurants with a CFSM to restaurants without a CSFM with the
number of risk factors cited during restaurant inspections as the dependent variable.
Table 3 shows the mean number of risk factors as a function of whether the restaurant had
a CFSM or not. The independent-sample t test was statistically significant, t (199) = -
13.46, p < .001. Therefore, the first null hypothesis of this study was rejected and it was
concluded that there was a statistically significant difference between restaurants that

have a CFSM and restaurants that do not have a CFSM on the number of risk factors
cited during restaurant inspections. Specifically, the means in Table 3 show that
restaurants with a CFSM tended to have more risk factors than (M = 1.28, SD = .58) than
restaurants without a CFSM (M = .41, SD = .84).
Table 3
Results From Independent-Sample t Test Comparing Restaurants With a CFSM and
Without a CFSM in Terms of the Number of Risk Factors (N = 1,547)
Group
M
SD
t
df
p
Without a CFSM
.41
.84
-13.46
199
< .001
With a CFSM 1.28 .58
Research Question 2
The second research question of this study were: Is there a statistically significant
difference between major restaurant chains and independent restaurants on the number of
risk factors cited during restaurant inspections? The corresponding hypotheses was:
H02: There is not a statistically significant difference between major restaurant
chains and independent restaurants in the number of risk factors cited during restaurant
inspections.
HA2: There is a statistically significant difference between major restaurant chains
and independent restaurants in the number of risk factors cited during restaurant
inspections.
For this null hypothesis, an independent-sample t test was performed with the
number of risk factors cited during restaurant inspections as the dependent variable and

the type of restaurant (chain vs. independent) as the independent variable. Table 4 shows
the results from the independent-sample t test and the mean number of risk factors as a
function of the type of restaurant. The independent-sample t test was statistically
significant, t (1544) = 2.62, p = .009. Therefore, the second null hypothesis was rejected,
and it was concluded that there was a statistically significant difference between major
restaurant chains and independent restaurants on the number of risk factors cited during
restaurant inspections. The means in Table 4 show that independent restaurants tended to
have a higher number of risk factors (M = 1.22, SD = .73) than chain restaurants (M =
1.13, SD = .60).
Table 4
Results From Independent-Sample t Test Comparing Chain Restaurants and Independent
Restaurants in Terms of the Number of Risk Factors (N = 1,547)
Group
M
SD
t
df
p
Independent restaurant
1.22
.73
2.62
1544
.009
Chain restaurant 1.13 .60
Research Question 3
The third research question of this study were: Is there a statistically significant
difference between restaurants that have a CFSM and restaurants that do not have a
CFSM on the restaurant food safety score identified on restaurant inspections? For this
research question, the null and alternative hypotheses was:

H01: There is not be a statistically significant difference between restaurants that
have a CFSM and restaurants that do not have a CFSM in the restaurant food safety score
identified on restaurant inspections.
HA1: There is a statistically significant difference between restaurants that have a
CFSM and restaurants that do not have a CFSM in the restaurant food safety score
identified on restaurant inspections.
An independent-sample t test was performed to compare restaurants with a CFSM
to those without a CFSM in terms of the food safety scores identified on restaurant
inspections. Table 5 shows the mean food safety score for each group and the results
from the independent-samples t test. The t test was statistically significant, t (201) =
2.07, p = .040. The third null hypothesis of this study was therefore rejected, and it was
concluded that there was a statistically significant difference between restaurants that had
a CFSM and restaurants that did not have a CFSM on the restaurant food safety score
identified on restaurant inspections. As seen in Table 5, restaurants without a CFSM
tended to have higher food safety scores (M = 87.08, SD = 10.12) than restaurants with a
CFSM (M = 85.46, SD = 7.19).
Table 5
Results From Independent-Sample t Test Comparing Restaurants With a CFSM and
Without a CFSM in Terms of the Food Safety Scores (N = 1,547)
Group
M
SD
t
df
p
With a CFSM
87.08
10.12
2.07
201
.040
Without a CFSM 85.46 7.19

Research Question 4
The fourth research question were: Is there a statistically significant difference
between major restaurant chains and independent restaurants in the restaurant food safety
score identified on restaurant inspections? The null and alternative hypotheses
corresponding to this research question was:
H02: There is not a statistically significant difference between major restaurant
chains and independent restaurants in the restaurant food safety score identified on
restaurant inspections.
HA2: There is a statistically significant difference between major restaurant chains
and independent restaurants in the restaurant food safety score identified on restaurant
inspections.
To test the null hypothesis, an independent-sample t test was performed to
compare major restaurant chains to independent restaurants on the food safety scores
identified on restaurant inspections. Table 6 shows the results for the independentsamples
t test, which was statistically significant, t (1540) = -4.25, p < .001. Thus, the fourth null
hypothesis of this study was rejected, and it was concluded that there was a statistically
significant difference in food safety scores between major restaurant chains and
independent restaurants. The means in Table 6 show that independent restaurants tended
to have lower food safety scores (M = 84.94, SD = 8.40) than chain restaurants
(M = 86.54, SD = 6.35).
Table 6
Results from Independent-Sample t Test Comparing Chain Restaurants and Independent
Restaurants in Terms of Food Safety Scores (N = 1,547)

Group
M
SD
t
df
p
Independent restaurant
84.94
8.40
-4.25
1540
< .001
Chain restaurant 86.54 6.35
Supplemental Analyses
In addition to the analyses performed to provide specific answers to the research
questions of this study, several supplemental analyses were performed. It was of interest
to determine the extent to which the results from the research questions would vary if the
district for each restaurant was taken into account. Therefore, a series of factorial
ANOVAs were performed similar to the first set of analyses but including district as a
second independent variable in each analysis. Table 7 shows the means that will be
compared in the subsequent analyses.
Table 7
Mean Number of Risk Factors and Food Safety Scores as a Function of District, Having a
CFSM, and Type of Restaurant (N = 1,547)
Central South North
M SD M SD M SD
Number of risk factors
1.14
.60
1.31
.79
1.15
.65
Presence of a CFSM
No
.36
.68
.32
.84
.53
1.00

Yes
1.24
.50
1.42
.71
1.23
.54
Type of restaurant
Independent
1.21
.63
1.29
.84
1.20
.73
Chain
1.07
.57
1.34
.73
1.06
.46
Food safety scores
86.40
7.41
84.28
9.09
85.70
6.45
Presence of a CFSM
No
87.37
9.94
86.47
12.14
87.10
9.07
Yes
86.27
6.99
84.04
8.67
85.51
6.00
Type of restaurant
Independent
85.64
8.28
83.78
10.12
85.02
7.20
Chain
87.11
6.43
84.93
7.57
86.92
4.58
The first analyses was performed to examine the difference between restaurants
that have a CFSM and restaurants that do not have a CFSM from the three districts on the
number of risk factors cited during restaurant inspections. Therefore, a 2 (CFSM or not)
by 3 (districts) factorial ANOVA was performed with the number of risk factors cited
during restaurant inspections as the dependent variable. Table 8 shows the results from
this ANOVA. The main effect for district was not statistically significant, F(2, 1541) =
1.25, p = .286. This indicated that overall the number of risk factors did not differ
significantly between Central, South , and North districts. The main effect for presence
of a CFSM was statistically significant, F(1, 1541) = 315.30, p < .001. This confirmed

the result from the independent samples t test performed for the first research question
where it was found that restaurants with a CFSM tended to have more risk factors than
(M = 1.28, SD = .58) than restaurants without a CFSM (M = .41, SD = .84).
Table 8
Results From Factorial ANOVA with Number of Risk Factors as the Dependent Variable
and District and Presence of a CFSM as the Independent Variables (N = 1,547)
Effect
Sum of
Squares
df
Mean
Squares
F
p
District
.92
2
.46
1.25
.286
Presence of a CFSM
116.44
1
116.44
315.30
<.001
District by Presence of a CFSM
3.47
2
1.73
4.70
.009
Error
569.10
1541
.37
The interaction between region and presence of a CFSM was also statistically
significant, F(2, 1541) = 4.70, p = .009. This indicated that the difference between
restaurants with a CFSM and restaurants without a CFSM varied for the three districts .
The top portion of Table 7 shows the means for district and presence of a CFSM, but
Figure 2 was created to aid in the interpretation of the statistically significant interaction.
From this figure it can be seen that the difference in the number of risk factors between
restaurants with a CFSM and without a CFSM was larger in South district than in Central
district or North district. Thus, while restaurants with a CFSM tended to have more risk
factors than restaurants without a CFSM in all regions, this was especially true in South
district.
Figure 2. Number of risk factors as a function of district and presence of a CFSM.
The second supplemental analysis was performed to determine if there were
differences between major restaurant chains and independent restaurants from the three
districts on the number of risk factors cited during restaurant inspections. Table 9 shows
the results from this ANOVA. The main effect for district was statistically significant,
F(2, 1541) = 9.84, p < .001. This differed from the results from the prior ANOVA where
the main effect for district was not statistically significant. In the results shown in Table
9, the statistically significant main effect for district indicated that the number of risk
factors was somewhat lower for Central district (M = 1.14, SD = .60) and North district
(M = 1.15, SD = .65) when compared to South district (M = 1.31, SD = .79).
Table 9
Results From Factorial ANOVA with Number of Risk Factors as the Dependent Variable
and District and Type of Restaurant as the Independent Variables (N = 1,547)
Effect
Sum of
Squares
df
Mean
Squares
F
p
0
0.2
0.4
0.6
0.8
1
1.2
1.4
1.6
Central
South
North
No CFSM
CFSM
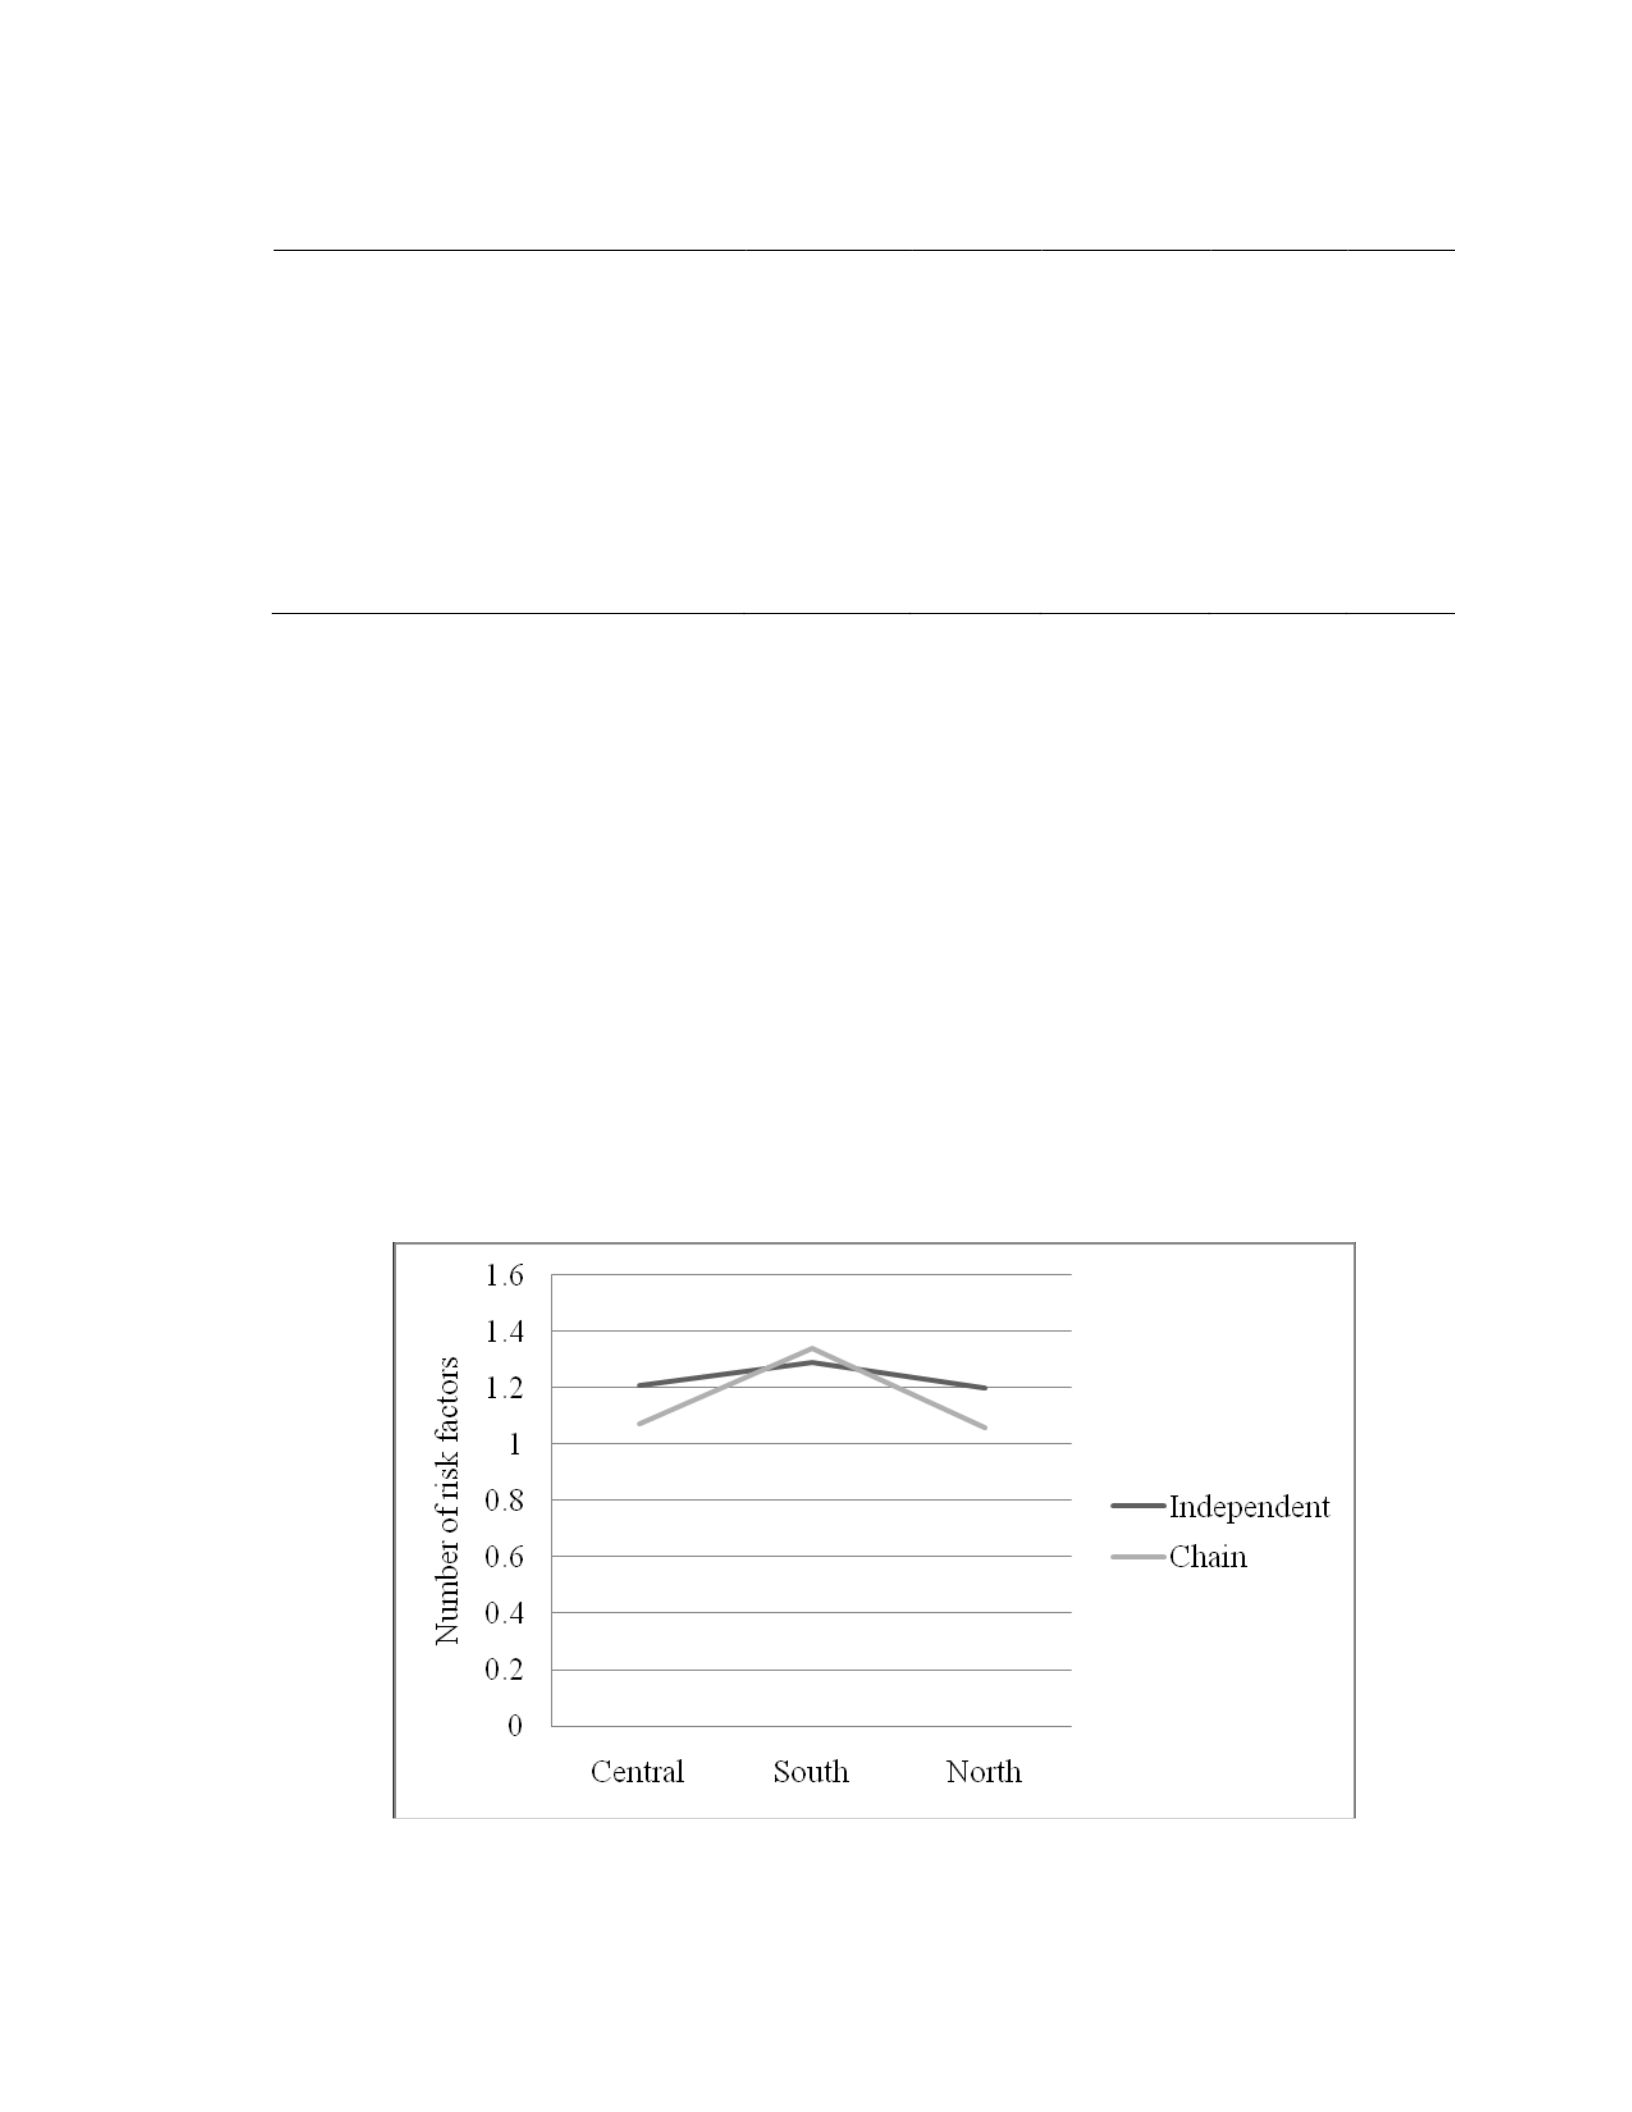
District
8.76
2
4.38
9.84
<.001
Type of Restaurant
1.81
1
1.81
4.06
.044
District by Type of Restaurant
2.44
2
1.22
2.75
.065
Error
685.95
1541
.45
The main effect for type of restaurant was also statistically significant, F(1, 1541)
= 4.06, p = .044. This confirmed the results from the second research question where it
was shown that independent restaurants tended to have a higher number of risk factors
than chain restaurants. The interaction between district and type of restaurant was not
statistically significant, F(2, 1541) = 2.75, p = .065. Figure 3 shows that the for South
district chain restaurants had slightly more risk factors whereas for Central district and
North district independent restaurants has slightly more risk factors, but this trend was not
statistically significant.
Figure 3. Number of risk factors as a function of region and type of restaurant.

The third supplemental analysis was performed to determine if there was a
statistically significant difference between restaurants that have a CFSM and restaurants
that do not have a CFSM from the three districts on the restaurant food safety score
identified on restaurant inspections. Table 10 shows the results from this analysis. The
main effect for district was not statistically significant indicating that the food safety
scores for restaurants from the three regions did not differ, F(2, 1541) = 1.96, p = .141.
Table 10
Results From Factorial ANOVA with Food Safety Scores as the Dependent Variable and
District and Presence of a CFSM as the Independent Variables (N = 1,547)
Effect
Sum of
Squares
df
Mean
Squares
F
p
District
223.56
2
111.78
1.96
.141
Presence of a CFSM
423.12
1
423.12
7.43
.006
District by Presence of a CFSM
40.70
2
20.35
.36
.700
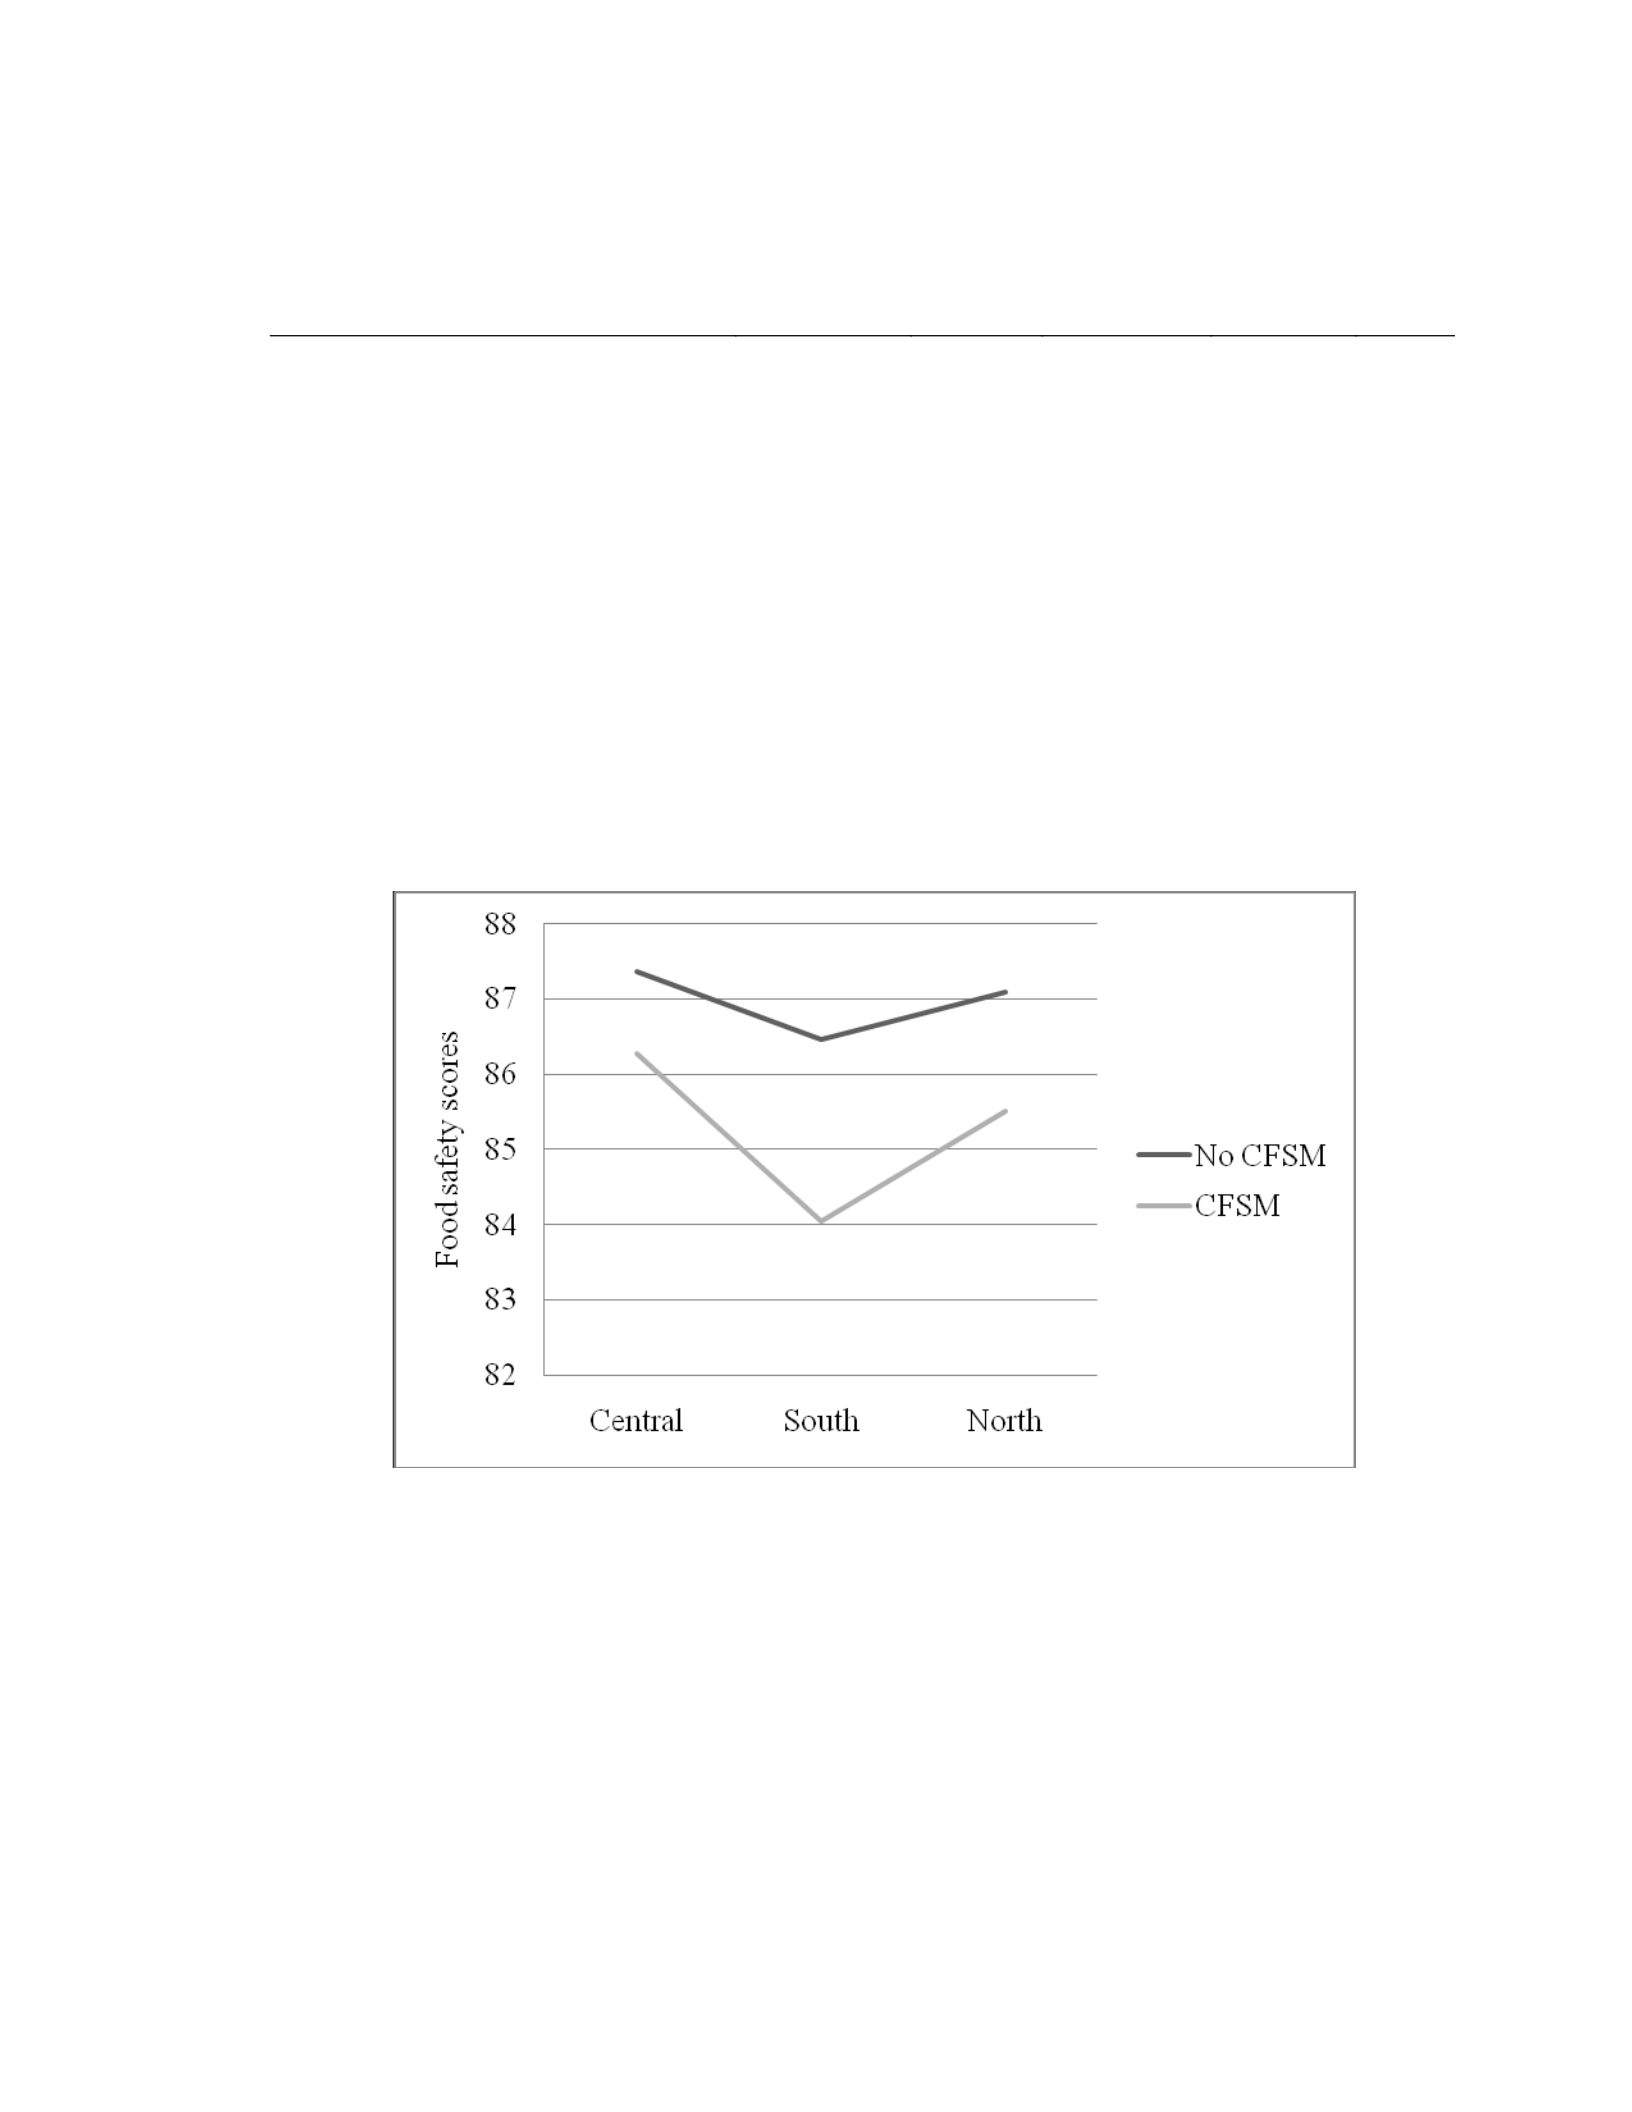
Error
87794.25
1541
56.97
The main effect for presence of a CFSM was statistically significant, F(1, 1541) =
7.43, p = .006. This confirmed the result from the third research question where it was
concluded that restaurants without a CFSM tended to have higher food safety scores (M =
87.08, SD = 10.12) than restaurants with a CFSM (M = 85.46, SD = 7.19). The
interaction between district and presence of a CFSM was not statistically significant, F(2,
1541) = .36, p = .700, and Figure 4 shows that the difference between restaurants with a
CFSM and without a CFSM was consistent for the three districts.
Figure 4. Food safety scores as a function of region and presence of a CFSM.
The fourth and final supplemental analysis was performed to determine if there
was a statistically significant difference between major restaurant chains and independent
restaurants from the three districts in the restaurant food safety score identified on
restaurant inspections. Table 11 shows the results from this ANOVA. The main effect for
district was statistically significant, F(2, 1541) = 8.81, p < .001. This indicated that the

mean food safety scores were highest for Central district (M = 86.40, SD = 7.41)
followed by North district (M = 85.70, SD = 6.45), with scores in South district being the
lowest (M = 84.28, SD = 9.09).
Table 11
Results From Factorial ANOVA with Food Safety Scores as the Dependent Variable and
District and Type of Restaurant as the Independent Variables (N = 1,547)
Effect
Sum of
Squares
df
Mean
Squares
F
p
District
998.88
2
499.44
8.81
<.001
Type of Restaurant
808.98
1
808.98
14.28
<.001
District by Type of Restaurant
30.14
2
15.07
.27
.766
Error
87310.02
1541
56.66
The main effect for type of restaurant was also statistically significant, F(1, 1541)
= 14.28, p < .001. This confirmed the results from the fourth research question where it
was concluded that independent restaurants tended to have lower food safety scores (M =
84.94, SD = 8.40) than chain restaurants (M = 86.54, SD = 6.35). The interaction
between district and type of restaurant was not statistically significant, F(2, 1541) = .27, p
= .766, and Figure 4 shows that the difference between independent restaurants and chain
restaurants was relatively consistent for the three districts.
Figure 5. Food safety scores as a function of region and type of restaurants.
Summary of Findings
The results from the analyses of the four research questions were presented in this
chapter. All four null hypotheses were rejected. The first research question were: Is there
a statistically significant difference between restaurants that have a CFSM and restaurants
that do not have a CFSM in the number of risk factors cited during restaurant
inspections? The results showed that restaurants with a CFSM tended to have more risk
factors than restaurants without a CFSM. The second research question of this study
were: Is there a statistically significant difference between major restaurant chains and
independent restaurants in the number of risk factors cited during restaurant inspections?
82
83
84
85
86
87
88
Central
South
North
Independent
Chain

The analyses indicated that chain restaurants tended to have a lower number of risk
factors than independent restaurants.
The third research question of this study were: Is there a statistically significant
difference between restaurants that have a CFSM and restaurants that do not have a
CFSM in the restaurant food safety score identified on restaurant inspections? The results
showed that restaurants without a CFSM tended to have higher food safety scores than
restaurants with a CFSM. The fourth and final research question of this study were: Is there
a statistically significant difference between major restaurant chains and independent
restaurants in the restaurant food safety score identified on restaurant inspections? Chain
restaurants tended to have higher food safety scores than independent restaurants.
Supplemental analyses were also performed to examine the potential effect of
district, and several conclusions were drawn. First, the results for the four research
questions were confirmed in all four of the supplemental ANOVAs performed. That is,
even when district was included in the analysis, the results from the four research
questions held. Second, there were some differences between the districts such as the
finding that the number of risk factors was somewhat lower for Central district and North
district when compared to South district. Similarly, food safety scores were highest for
Central district and North district but lower in South district. However, both of these
regional effects should be interpreted cautiously because the main effect for district was
statistically significant in both ANOVAs involving the type of restaurant but not
statistically significant in both ANOVAs involving the presence or absence of a CFSM.
In addition, one of the interactions involving district was statistically significant.
Specifically, the interaction between district and presence of a CFSM was statistically

significant indicating that although restaurants with a CFSM tended to have more risk
factors than restaurants without a CFSM in all districts, this was especially true in South
district. Chapter 5 presents a discussion of these findings, and recommendations are
offered for the restaurant industry and future research in this area.
Chapter 5: Discussion, Conclusions, and Recommendations This study
was conducted to fill a gap in the literature to determine whether having a CFSM had an
effect on risk factors that are associated with food-borne illness. Literature reviewed for
this study addressed critical and noncritical risk factors, food safety practices,
effectiveness of food safety training, and the impact of having a CFSM. Findings in the
literature were limited to whether or not a CFSM had an effect on risk factors and food
safety scores. The problem examined in this study was whether there is a relationship
between having a CFSM and the number of risk factors cited on restaurant inspections in
Georgia; whether the restaurant operation type (i.e., chain vs. independent restaurant) has
an impact of the number of risk factors cited on restaurant inspections; whether there is a
relationship between having a CFSM and the restaurant food safety score identified on
restaurant inspections; and whether the restaurant operation type (i.e., chain vs.
independent restaurant) have has an impact on the restaurant food safety score.
This chapter contains a discussion of the results from the previous chapter.
Interpretation of Findings
In the following section, these findings are interpreted in the context of past
research in this area and the theoretical framework of this study.

Interpretation in the Context of Previous Research
Managers are certified in food safety to educate them about the relationship
between risk factors that lead to food-borne illnesses and food safety practices. Several
studies have examined the relationship among certified managers, risk factors, and
restaurant scores and found that scores and the number of risk factors improved with the
presence of a CFSM (Cates et al., 2009; Cotterchio et al., 2009; Hedberg et al., 2006).
However, in a study conducted by Mathis et al. (1994), there was no significant
association between violations cited on food safety inspections and food safety training.
The findings from this current study showed a statistically significant difference between
restaurants with a CFSM and restaurants without a CFSM. Results revealed that
restaurants that had a CFSM had more risk factors than restaurants without a CFSM.
Likewise, Kassa et al. (2010) found that certification did not impact the number of
violations cited on food inspection reports. Also, restaurants with a CFSM had lower food
safety scores than restaurants without a CFSM. Cates et al. (2009) revealed in their study
that certified managers were less likely to have a critical violation; however, certified
managers were not effective at controlling temperature and time violations, which are risk
factors associated with food-borne illness. It is possible that managers are not
implementing the tools and practices learned in food safety training. In some cases,
managers may not feel that food safety is important.
Managers may not have an adequate amount of staff to send to food safety
training to make sure that someone is certified on all shifts. When managers are dealing
with turnovers and inadequately trained employees, food safety may not be a top priority

(Enz, 2004). This could lead to food being mishandled, which increases the chance for
critical violations.
Another possibility is that managers of independent restaurants view food safety
as more important due to the fact that they work in small businesses (sometimes family
owned) that they value. In most independent restaurants, the staff is very small and often
consists of family, with all working toward a common goal. Cates et al. (2009) suggested
that the size of the establishment may affect the number of critical violations. Larger
establishments when compared to smaller establishments are more likely to be cited for
critical violations (Cates et al., 2009). This could be due to the fact that larger
establishments have a larger volume of customers than smaller establishments do,
increasing the chance for more critical violations. How management views food safety,
employees’ knowledge of food safety, and how busy a restaurant is all have an influence
on food safety practices.
There was a statistically significant difference between chain restaurants and
independent restaurants for risk factors and food safety scores. Analyses showed that
chain restaurants had fewer risk factors and higher food safety scores than independent
restaurants. Murphy et al. (2011) examined the association between manager food safety
certification and inspection results among chain and independent restaurants and found
results similar to those reported here. Kasssa et al. (2010) suggested that restaurants that
are considered chains usually have their own internal inspectors and corporate guidelines
to follow that are usually more stringent than the rules and regulations of local health
departments.

For example, a study by Lynch et al. (2003) revealed that managers who received
corporate training along with training from the health department were more
knowledgeable in food safety practices. In addition, the majority of fast food restaurant
owners own more than one restaurant, most likely part of a chain, and they have specific
food safety procedures to follow and are able to offer food safety training to more
employees (Cates et al., 2009). Also, fast food restaurants’ practices are standardized and
usually involve the use of specialized equipment, thus minimizing room for error (Kassa
et al., 2010).
In this study, it was found that food safety practices are being followed and
implemented in chain restaurants more often than in independent restaurants, as
evidenced by the number of risk factors. It is possible that chain restaurants have more
support and available resources from a corporation than independent restaurants do, and
chain restaurants are more likely to have corporate support for food safety training.
Interpretation in the Context of the Theoretical Framework
The epidemiological triangle model, shown in Figure 1 (p. 11), was used as the
theoretical framework for this study. In the model, there are three corners: agent,
environment, and host. The agent causes the disease, the host harbors the disease, and the
environment allows for transmission of the disease. The epidemiological triangle is
frequently used in public health settings to study infectious diseases and how they are
spread (Merrill, 2012); for this current study, the model was applied to a restaurant setting
to determine whether CFSMs had an effect on risk factors that lead to food-borne
illness.

The results from this study show that restaurants with a CFSM compared to
restaurants without a CFSM had more risk factors and lower food safety scores. It is
possible that food service managers are being certified but are not implementing food
safety practices among employees to break the chain of transmission by correcting unsafe
food practices. Cates et al. (2009) revealed in their study that certified kitchen managers
were not effective at controlling time and temperature violations, such as those related to
proper cooling, cooking, and reheating temperatures. A telephone survey conducted on
food handlers by Green et al. (2005) found that 60% did not wear gloves while handling
ready-to-eat foods, 23% did not follow proper hand-washing, and 33% did not change
gloves when switching tasks. All of these factors play an important role in the
transmission of food-borne illness in restaurants. Findings suggest that food safety
practices learned and recommended from certification do not always translate into
implementation. The purpose of having a CFSM is that someone has been through food
safety training and has the knowledge and skills necessary to demonstrate food-borne
illness prevention techniques. Thus, CFSMs have the significant role of communicating
to their employees information learned in food safety training about recommended food
safety practices that reduce food-borne illness.
Also, chain restaurants had a lower number of risk factors and higher food safety
scores when compared to independent restaurants. In a survey conducted by Roberts and
Sneed (2003) on managers of independent restaurants in Iowa, researchers found that
43.2% of the managers of independent restaurants did not have guidelines for cleaning
and sanitizing equipment, 24% did not have a hand-washing policy, and 46% had no
measures for checking temperatures on food received. In a similar study interviewing

involving interviews with sanitarians in Iowa and Kansas, Robert, Barrett, and Sneed
(2005) found that 80% of the respondents indicated that independent restaurants did not
have guidelines for cleaning and sanitizing equipment, 82% did not have a hand-washing
policy, and 90% had no measures on checking temperatures on food received. Chain
restaurants had better ratings with sanitarians; only 37% did not have guidelines for
cleaning and sanitizing equipment, 6% did not have a hand-washing policy, and 47% had
no measures on checking temperatures on food received. The reason chain restaurants
may perform better could be that managers of chain restaurants have corporate support
and funds to offer more extensive food safety training. In addition, incentives may be
offered to managers for performing well. Findings indicate that further research is needed
in food safety training efforts and education among independent restaurants.
Limitations
There were several limitations to this study. The first limitation of this study was
the reliance on archival data. This study used existing publically available secondary data,
and no new data were collected. Out of 18 health districts in Georgia, this study examined
health inspection reports from only North, Central, and South health districts that were in
operation in 2013. Georgia food rules and regulations are not comparable to those of
other health jurisdictions in other states, as food rules and regulations vary by state.
Another limitation to the study was that the views of health inspectors may have
an effect on the number of critical violations documented because of personal
interpretation. In the State of Georgia, all health inspectors go through standardization,
but other factors such as the relationship with the manager/owner, years of experience,
and bias may impact an inspector’s ability to document critical violations (Medeiros &

Wilcox, 2006). All of these factors play a role and impact critical violations documented
on food inspection reports.
Recommendations for Further Research
Several recommendations for future studies based on the results have been
developed. Future researchers could explore other programs that address risk factors,
such as Risk Control Plans and HACCP plans. Analyzing a Risk Control Plan might be
useful and provide managers with information in regard to whether or not food safety
practices that decrease critical violations are being followed. In addition, a HACCP plan
allows managers to create a plan that incorporates food safety principles. Each step is
monitored in the flow of the food, from purchase all the way to service, to ensure that
food safety practices are intact.
Future studies comparing different times of day when health inspections are
conducted may be useful. A trend in violations may be shown during certain times of day.
A study like this could be useful and provide information about what type of violations
are likely to occur during the daily operation of a facility. By documenting certain
violations and what time they occur during operation, it is possible to create an
intervention using data. This could help managers identify weaknesses within their
operation and implement corrective actions.
An additional recommendation for future research is based on the results from the
supplemental analyses. These results showed that district did have an impact on the
number of risk factors and food safety scores with restaurants from South district tending
to perform more poorly than restaurants from Central district and North district. The
reasons for these differences are not clear, and future researchers may wish to explore

these differences in more detail. One interesting finding in the current study was that in
South district chain restaurants tended to have more risk factors than independent
restaurants whereas in Central district and North district it was independent restaurants
that had more risk factors. Future research into these trends may be useful in
understanding these effects.
Social Change Implications
The positive social change impact of this study lies in its potential to aid managers
in helping food workers in understanding (a) how food becomes unsafe and (b) important
prevention measures to keep food safe, as well as recognizing (c) the importance of food
safety and (d) the risk factors associated with food-borne illness in restaurants. By
contributing to a better understanding of how food becomes unsafe if food handlers are
not practicing food safety, the results of this study could aid in the design of food safety
training programs to increase knowledge and understanding of food safety practices. It is
of vital importance to understand how food becomes unsafe if food handlers do not
handle food correctly. Because managers have the responsibility of ensuring food safety
in their operation, it is important to make sure that their staff are trained in measures to
keep food safe, are retrained in food safety regularly, and are monitored to make sure
procedures are being followed. This allows managers to correctly implement food safety
practices in their operation, demonstrating active managerial control.
With an increase of independent restaurants, it is important that food is being
prepared safely. Results from the study show food safety training and interventions aimed
toward independent restaurant managers are needed. Programs could help independent
restaurant managers as well as employees understand the importance of safe food

handling. Managers and employees alike should be knowledgeable about food safety
practices and how to safely prepare and handle food. Having someone available to help
independent managers understand the food rules and regulations to allow for effective
food safety training could decrease critical violations within independent restaurants.
Conclusions
This study examined the relationship between having a CFSM and the number of
risk factors cited on inspection reports, operation type (chain vs. independent) had an
impact on the number of risk factors, the relationship between having a CFSM and the
restaurant food safety score, and whether restaurant operation type had an impact on
restaurant food safety score in three health districts located in Georgia in 2013. In a FDA
(2009c) report, 65% of food-borne illness outbreaks in U.S. restaurants were linked to
food employees. Jones and Angulo (2006) and the CDC (2006) reported that 52% to 59%
of food-borne illnesses in the United States are caused by restaurants. Restaurant
managers depend on their employees to prepare and handle food safely. Therefore, it is
important that managers are knowledgeable in food safety and help their food service
employees understand the importance of food safety in the prevention of food-borne
illness.
There were several key findings. While restaurants with a CFSM had significantly
more risk factors than restaurants without a CFSM, the number of risk factors for chain
restaurants was significantly lower than that for independent restaurants. There was a
significant difference between food safety scores for restaurants with a CFSM and
restaurants without a CFSM. Restaurants with a CFSM had lower food safety scores than

restaurants without a CFSM. For chain restaurants, I also found a significant difference in
food safety scores on inspection reports compared to independent restaurants.
Food safety training and education are key components in the effort to minimize
food-borne illness in restaurants. It is assumed that training and education have a
significant effect on critical violations and food-borne illness outbreaks. Managers who
are certified in food safety are perceived to be more knowledgeable in food safety
practices and have the skills to implement prevention measures to ensure that food safety
measures are being met. However, the literature reviewed in Chapter 2 demonstrated that
results have been inconclusive in regard to the effectiveness of manager training in
preventing or decreasing critical violations. For example, the findings from the current
study showing that restaurants with a CFSM had more risk factors and lower food safety
scores contradicted other findings that restaurants with a CFSM had significantly higher
inspection scores and a decrease in critical violations compared to restaurants without a
CFSM (Cotterchio et al., 1998; Kassa et al., 2010). This study filled a gap in the literature
as to whether the presence of a CFSM has an effect on risk factors and food safety scores,
and whether operation type (chain vs. independent) has an impact on risk factors and food
safety scores, in addition to providing information for positive social change toward the
development of food safety training to reduce the occurrence of critical violations in
restaurants. Exploring the effectiveness of manager certification is important for food
safety and the protection of public health, and further research is needed.

