


1
Section 1: Foundation of the Study
Dual-eligible beneficiaries are those entitled to both federal and state health care
benefits (Eggbeer, Bowers, & Morris, 2013). The dual-eligible population accounts for a
disproportionate share of state and federal health care expenditures (Gimm, Blodgett, &
Zanwar, 2016). Moreover, dual-eligible beneficiaries have a greater likelihood of poor
health outcomes related to multiple chronic conditions, mental illness, and functional
limitations than beneficiaries with single coverage (Eggbeer et al., 2013). Policymakers
focused on reducing health care costs by improving the poor coordination of state and
federal health benefits (Gimm et al., 2016). Health care leaders describe the dual-eligible
market as a multibillion dollar opportunity to reduce health cost by using care
coordination programs (Eggbeer et al., 2013).
The triple aim model (TAM) of reducing per capita health care costs, improving
patient experience, and providing population health is a national framework to transform
health care at the social and business levels (Bodenheimer & Sinsky, 2014). Improving
coordination may require health care leaders to assess current processes to determine
appropriate resource allocation to realize the financial benefit of program
implementation. Providing financial justification for health care interventions is a
challenge for health care leaders (Wilf-Miron, Bolutin, Gordon, Porath, & Peled, 2014).
Some health care leaders struggle with reflecting the benefit of investing in care
coordination programs (Perry & Stevens, 2013). Wilf-Miron et al. (2014) indicated the
need for additional research on presenting the financial impact of implementing care
coordination programs. The aim of this study was to explore strategies health care leaders

2
use to improve corporate financial investment in care coordination programs that include
TAM objectives.
Background of the Problem
The older adult population with both federal and state health care benefits is
accountable for 39% of state expenditures and 31% of federal expenses (Gimm et al.,
2016). Eggbeer et al. (2013) indicated the total health care costs associated with the dual-
eligible population totaled $320 billion. The enrollment of dually eligible beneficiaries in
a managed care organization can save the public health care programs an estimated $13
billion in health care cost over a 5-year period (Frank, 2013). Therefore, policy leaders
authorized 3-year dual demonstration programs that outsourced the care coordination of
the dual-eligible beneficiaries to managed care plans (Eggbeer et al., 2013). Sixty
managed care plans in 10 states received a capitated, risk-adjusted payment to provide
services for dual-eligible beneficiaries (Craver, Cuellar, & Gimm, 2016). Managed care
leaders within a capitated payment model set care coordination program cost at $150 to
$195 per beneficiary per month (Eggbeer et al., 2013). The change in the regulatory
landscape challenged health care leaders to provide sustainable solutions to address the
$20 billion loss associated with the lack of care coordination for the dual population
(Eggbeer et al., 2013). According to Hendrikx et al. (2016), leaders pursue TAM
objectives to ensure a sustainable health care system. Moreover, TAM goals of achieving
population health, reducing per capita costs, and improving patient satisfaction are the
framework defining the systematic social and business changes required in the health care
industry (Bodenheimer & Sinsky, 2014). According to Miranda, Ferranti, Strauss,

3
Neelon, and Califf (2013), health care leaders use TAM objectives to define the
transformation of the health care system. Health care leaders must take an individualized
approach to developing a business strategy for care coordination programs based on the
drivers of profit margin and the mission of the organization (Perry & Stevens, 2013). The
results of this study may impact the field of business by providing strategies for health
care leaders in the position of manager, director, and vice president to improve corporate
financial investment in care coordination programs that include TAM objectives.
Problem Statement
Care coordination programs for dual-eligible beneficiaries cost between $150 and
$195 per enrollee per month (Eggbeer et al., 2013). Health care leaders must limit
allocation to care coordination programs to $125 to $150 per member per month to
realize net savings (Brown, Peikes, Peterson, Schore, & Razafindrakoto, 2012). The
general business problem was a lack of financial investment in care coordination
programs by managed care organizations, which results in loss of profitability for the
organization. The specific business problem was that some health care leaders in the
position of manager, director, or vice president lack strategies to improve corporate
financial investment in care coordination programs that include TAM objectives.
Purpose Statement
The purpose of this qualitative single-case study was to explore the strategies that
health care leaders use to improve corporate financial investment in care coordination
programs that include TAM objectives. The target population was health care leaders in
the role of vice president or higher from one health care organization with experience

4
implementing strategies to improve corporate financial investment for care coordination
programs that included TAM objectives. The geographical region was Southern
California. Health care executives may consider the findings from this study as a
contribution to social change if recommendations improve the quality of care for the
dual-eligible population.
Nature of the Study
I selected the qualitative method for this study. Qualitative researchers can use
interviews to seek an understanding of the uniqueness of events from the perspective of
the participants, which extends beyond a comparison of variables (Stake, 2010). The
qualitative method was appropriate because I used interviews for an in-depth exploration
of a distinct event. Conversely, quantitative researchers use numerical data to test
hypotheses (Hanson, Balmer, & Giardino, 2011). The quantitative approach was not
appropriate because I did not intend to test hypotheses or use an experimental setting for
the study. In mixed-methods research, researchers combine qualitative and quantitative
methods when a single method is insufficient to provide a comprehensive understanding
of the topic or results require additional clarification (Wisdom, Cavaleri, Onwuegbuzie,
& Green, 2012). The mixed-methods approach was not appropriate because the
integrative approach would have complicated the scope of the study beyond the
collection of descriptive data to reflect the insights of the participants.
I used a case study design. Researchers can use interviews in a case study design
to conduct in-depth research on a contemporary event within the bounds of the case study
site (Yin, 2014). The case study design was appropriate because the objective of the study

5
was to conduct in-depth research of current strategies used by health care leaders to
garner financial support within the bounds a single organization. The ethnographic,
phenomenological, and narrative designs were not suitable for this study. Researchers use
the ethnographic design to understand the culture of the environment by engaging in
extended relationships with research participants (Wolcott, 1999). The objective of this
study was not to engage in an extended relationship with participants to gauge the culture
of the organization. According to Moustakas (1994), phenomenological researchers study
lived experiences of participants and the perceptions of those experiences. In this study, I
did not seek to provide an understanding of the lived experiences of the participants.
Finally, researchers using the narrative design provide a sequential account of the
participant’s personal stories regarding his or her life experience (Hays & Woods, 2011).
The narrative design was not appropriate because I did not take an account of a sequence
of events to tell a story.
Research Question
The central research question was as follows: What strategies do health care
leaders use to improve corporate financial investment in care coordination programs that
include TAM objectives? The interview questions included the following:
Interview Questions
1. What successful strategies did you use to improve corporate financial
investment in care coordination programs?
2. What strategies did you find worked best to improve corporate financial
investment in care coordination programs?

6
3. How did you communicate the corporate financial investment strategies to
executive leaders?
4. How did you evaluate the cost effectiveness of care coordination programs?
5. What are your recommendations to health care leaders pursuing care
coordination investments?
6. What other information can you share regarding this study?
Conceptual Framework
TAM, which was developed by Berwick and the Institute for Healthcare
Improvement in 2008, is a framework that provides the social and business constructs
required for health care transformation (Vetter, Boudreaux, Jones, Hunter, & Pittet,
2014). The key tenets of TAM are population health, reducing per capita health care
costs, and improving patient satisfaction (Miranda et al., 2013). According to
Whittington, Nolan, Lewis, and Torres (2015), leaders are successful in deploying TAM
when there is investment capacity to integrate the key tenets and alignment in the
organizational governance structure. The development of business strategies requires
leaders to align with the key corporate metrics driving the decisions of senior leaders
(Harvard Business Press, 2011).
Anderson and Bjarnadóttir (2016) posited that health care leaders face difficulty
in defining the cost effectiveness of care coordination programs due to variations in
program models. Likewise, Katon and Unützer (2013) indicated that defining the
financial structure at the organizational level is a hindrance in the adoption of new care
coordination models. According to Ory et al. (2013), TAM objectives are the measures of

7
successful care coordination implementation. Therefore, TAM was applicable because I
explored the strategies health care leaders use to improve corporate financial investment
in care coordination programs that included TAM objectives.
Operational Definitions
Capitated payment: Capitated payments are payments fixed per enrollee per
month (Quinn, 2015).
Care coordination: Care coordination is a set of activities to manage the health
care needs of a population, resulting in a cost saving (Scholz, 2015).
Corporate financial investment: Corporate financial investment is money
attributed to an asset with the expectation of an increase in the future value of the asset
(Chaysin, Daengdej, & Tangjitprom, 2016).
Dual-eligible: Dual-eligible beneficiaries are beneficiaries receiving federal and
state-sponsored health care benefits from a single source that integrates the financing and
delivery of care (Prindiville, 2013).
Managed Care Organization for the Older Adult (MCOOA): MCOOA is a
capitated, risk-adjusted organization that provides services to a defined older adult
population (Morley, Walsh, & Wilkin, 2013).
Risk adjustment: Risk adjustment is the process of adjusting payment to the
MCOOA based on the severity of illness for a beneficiary qualified for the federally
sponsored health care program (Hellander, Himmelstein, & Woolhandler, 2013)
Star quality rating: Star quality rating is the federal quality rating system that
rates MCOOA on a 1 to 5 rating scale (Reid, Deb, Howell, & Shrank, 2013).

8
Transition: Transition is the process of changing from one health care level to
another (Cleave et al., 2013).
Transitional care: Transitional care includes services provided to support
continuity of care between care transitions during a specified time interval (Verhaegh et
al., 2014)
Assumptions, Limitations, and Delimitations
Assumptions
Assumptions are the components of the study that validate the relevance of the
research topic (Thomas, Nelson, & Silverman, 2010). The underlying assumption of this
study was that health care leaders in the position of manager, director, or vice president
consider care coordination programs a viable solution to impacting costs within an
MCOOA. There was an assumption that the MCOOA leaders consider TAM objectives
of reducing per health care capita cost, improving patient experience, and improving
population health as the foundation for health care transformation. The next assumption
was that the inclusion criteria would allow me to identify participants with the knowledge
base to provide in-depth answers to the interview questions. Finally, I assumed that
participants would provide honest responses during the interview process.
Limitations
The limitations are the weaknesses of the study that are outside the control of the
researcher (Thomas et al., 2010). The single case study design limitations included
sample size and generalizability. According to Yin (2014), the single case study design
limits the study to a single unit of analysis, which may not represent the activities of other

9
organizations. In addition, the sample size in a single unit of study was a limitation.
Finally, documentation as a source of evidence was a limitation based on retrievability,
biased selectivity, reporting bias, and access (Yin, 2014).
Delimitations
According to Thomas et al. (2010), the delimitations are within the capacity of the
researcher to control and are used to identify the bounds of the study. I delimited the
study to participants with the breadth of knowledge and willingness to participate in the
study. The participants included leaders within a bounded managed care system delimited
to a single eastern county of Southern California. In addition, the case study site
contracted to provide care for beneficiaries receiving federally sponsored health care
benefits, state-sponsored benefits, employer-based benefits, dual-eligible beneficiaries,
and the uninsured. The delimitation was to the beneficiaries dually eligible for federal-
and state-sponsored health care benefits.
Significance of the Study
A challenge to the health care system in the United States is to convert a
fragmented system into one that focuses on reducing costs through integrated service
delivery, enhanced population health, and improved quality (Enthoven, 2016). TAM is
the framework defining the health care systematic changes required to control costs
(Bodenheimer & Sinsky, 2014). The core objectives of TAM include improving
population health, reducing the cost of health care, and improving patient satisfaction
(Bodenheimer & Sinsky, 2014). According to Fuse-Brown (2015), cost containment is a
critical component of the Affordable Care Act (ACA). The transformation of the

10
provision of care for the 10.2 million beneficiaries of federal and state health care reflects
the social and economic influence of the ACA (Craver et al., 2016). Therefore, health
care executives have an interest in strategies to control the cost for the dual-eligible
population because the population has a higher incidence of chronic conditions, social
needs, and mental health disorders (Zainulbhai, Goldberg, Ng, & Montgomery, 2014).
According to Murphy and Neven (2014), the cost of inpatient utilization has led to
national attention to care activities designed to reduce costs. Senior executives can have
an awareness of the need to develop innovative programs; however, leaders must present
an evidence-based business strategy to support the use of scarce resources (de Waal,
Beaumont, & Mitchell, 2013). The study of strategies for health care leaders to improve
the corporate financial investment in care coordination programs that included TAM
objectives may be valuable in maintaining the financial solvency of MCOOA, reducing
fragmentation of health care, and improving the quality of care to the older adult.
Contribution to Business Practice
The dual-eligible population accounts for 20% of the U.S. federal program
enrollment and approximately 40% of the total expenditures (Frank, 2013). Moreover, the
dual-eligible population has a greater incidence of emergency hospitalizations, chronic
conditions, homelessness, and frailty (Ortega, 2016). In the capitated model, the MCOOA
will receive a prospected, blended payment to manage services for beneficiaries
(Rahman, Keohane, Trivedi, & Mor, 2015). According to Kennedy (2013), beneficiaries
of federal and state health care programs spend $300 billion annually. Reinhard (2013)
identified an opportunity to increase market share and profitability for those MCOOA

11
with the capacity to integrate and coordinate care for the high-risk dual population.
Furthermore, Zainulbhai et al. (2014) indicated that new strategies to improve access,
control costs, improve the quality of care, and reduce barriers are essential to managing
the financial burden of the dual-eligible population. Health care leaders, however, may
not have the competencies to develop a business case presentation to support the
implementation of new strategies (de Waal et al., 2013). The results of this study may
contribute to efficient business practices by identifying the strategies aligned with TAM
objectives of reducing per capita costs. The results may also influence business practices
by providing strategies for health care leaders in the position of manager, director, or vice
president to gain access to corporate resources for the implementation of care
coordination programs.
Implications for Social Change
MCOOA accounts for 25% of the enrollment for beneficiaries with federal- and
state-sponsored health care benefits (Reid et al., 2013). Therefore, MCOOA could have a
positive effect on the federal health care program by improving the quality of care
(Newhouse & McGuire, 2014). Deficient care coordination during transitions from the
hospital to the community can lead to adverse outcomes and readmissions (Feltner et al.,
2014). Hodin (2013) indicated that fragmented care for dual beneficiaries has an adverse
influence on their overall health outcomes. The results of the current study may
contribute to positive social change by supporting TAM objectives of population health
and improved patient experiences. Furthermore, the results may have a positive impact on
social change by providing insight into the strategies health care leaders positioned in the

12
role of manager, director, or vice president use for care coordination programs designed
to impact the adverse outcomes experienced by the dual-eligible population.
A Review of the Professional and Academic Literature
There is an increased focus on preserving federal and state funding by
encouraging innovative approaches to improving the quality of care for the dual-eligible
population. However, care models must align with new payment structures and quality
initiatives for MCOOA sustainability. Health care leaders strategize on how to create a
business case for coordinated care programs when the traditional business model is not
applicable (Perry & Stevens, 2013). The focus of the current study was to explore the
strategies health care leaders use to improve the corporate financial investment in care
coordination programs that include TAM objectives. The literature review reflected the
core business implications for MCOOA to implement care coordination programs for the
dual-eligible population and the position of industry leaders.
I employed a systematic approach using journal articles, scholarly books, and
dissertations to guide the literature review. A gap existed in the literature on strategies for
leaders to garner financial support for care coordination programs for the dual-eligible
population. The gap may be due to the July 2014 implementation of integrated benefits
for the dual-eligible population. As illustrated in Table 1, the literature review included
246 publications, 87% with publication dates between 2013 and 2017. Of the 246
publications, the peer-reviewed articles accounted for 90%. The electronic databases
were EBSCOHost, Academic Search Complete, Science Direct, Thoreau, and ProQuest. I
also used the Google Scholar search engine. My strategy to extract relevant literature

13
started with a broad search of terms narrowed to a specific term search. First, the search
included triple aim, dual-eligible, readmission, care coordination, patient-centered
medical home, accountable care organization, Medicare Advantage, health care reform,
health care cost, Medicare costs, corporate sustainability, corporate social
responsibility, stakeholder theory, shareholder theory, Star ratings, medical loss ratio,
risk-adjustment managed care, qualitative research care coordination, qualitative
research health care, health care leadership, and health care leaders. Next, the specific
terms included cost of dual-eligible, Affordable Care Act, Financial Alignment Initiative,
triple aim objectives, population health, transition of care, business case, business case
health care, business case care coordination, cost-effectiveness of care coordination,
cost-benefit analysis, and care coordination return on investment. The results of the term
search guided the inquiry. Additionally, the linked articles feature within the electronic
databases contained resources for the literature review. As I cataloged references, themes
emerged to define the seven sections of the literature review. I organized the literature
review into these sections to present the analysis and synthesis of the literature based on
the focus of discussion: (a) comparative theories, (b) MCOOA, (c) Affordable Care Act,
(d) care coordination, (e) dual-eligible population, (f) readmissions, (g) relationship of
study to previous research.
Table 1
Source of Literature for the Literature Review
Total
Percentage
Peer reviewed articles 197 90%
Publication between 2013 and 2017 214 89%

14
Seminal books 16 7%
Comparative Theories
The comparative theories for critical analysis included TAM, corporate social
responsibility theory (CSRT), corporate sustainability theory (CST), stakeholder theory,
and shareholder theory. Bodenheimer and Sinsky (2014) indicated that TAM represents
the interdependent business and social objectives required to re-engineer the health care
system. Similarly, Eccles, Ioannou, and Serrafeim (2014) noted CST has interrelated
dimensions of social, economic, and ecological activities. The fundamental principles of
CSRT are the organization’s socially responsible activities (Husted, Montiel, &
Christmann, 2016). According to Eccles et al., maintaining a positive profit margin for
the shareholders in an environment free of fraudulent practices is the central social
obligation of organizations grounded in the shareholder theory. Conversely, stakeholder
theorists extended corporate accountability to shareholders and multiple stakeholders due
to the interrelated aspects of business and society (Queen, 2015).
Triple aim model. The conceptual framework guiding this study was TAM.
Health care researchers at the Institute for Healthcare Improvement (IHI) proposed TAM
in 2008 as a concept to address health care deficiencies (Whittington et al., 2015). TAM
is the health care framework defining the systematic changes required to control health
care costs (Bodenheimer & Sinsky, 2014). Moreover, the core objectives of TAM include
achieving population health, reducing the cost of health care, and improving patient
satisfaction (Bodenheimer & Sinsky, 2014). The researchers at the IHI posited that
societal changes were necessary to realize global transformation in the health care

15
structure (Whittington et al., 2015). Similarly, Miranda et al. (2013) indicated that leaders
use the TAM objectives to define health care system transformation.
Policymakers structured the ACA programs to make systematic changes from
volume-based health care to a structure grounded in the value of health care (Cason,
2015). Strong, Hanson, Magnusson, and Neiger (2015) indicated that the ACA provisions
align with the goal of achieving TAM objectives. Therefore, health care leaders use the
TAM model to define the success of health care reform initiatives (Katon & Unützer,
2013). Strong et al. noted that the strategies of implementing TAM include isolating a
population, defining measures of success, achieving system-level outcomes, and
providing an expeditious evaluation of effectiveness. However, Hendrikx et al. (2016)
indicated that differences in the industry definitions of TAM objectives cause variation in
the means of measuring successful implementation. Eapen, Lauer, and Temple (2014)
posited that measuring the achievement of TAM objectives required clinical trials with
adequate sample sizes to measure clinical outcomes. According to Panzer et al. (2013),
measuring TAM objectives requires health care leaders to define the benchmark
performance for each measure.
Triple aim objectives. The components of TAM include reducing per capita
costs, achieving population health, and improving the patient experience (Bodenheimer &
Sinsky, 2014). Vetter et al. (2014) indicated the cost of health care in the United States
would represent 19.3% of the GDP by 2019. Similarly, Jackson et al. (2013) posited that
the United States spends a greater percentage of the GDP on health care than any other
country; however, this does not equate to higher quality outcomes. TAM is integral in

16
addressing health care waste and increasing costs (Coyne et al., 2014). However, provider
payment models lack incentives for lowering the per capita cost of health care
(Whittington et al., 2015). Gage and Albaroudi (2015) posited that the focus of
policymakers shifted from cost control to improving the value of health care.
Population health encompasses the clinical outcomes of a defined group of
individuals (Kindig & Isham, 2014). Whittington et al. (2015) pointed out that health care
leaders must engage in completing a population assessment and choose populations
whereby the three objectives of TAM apply. Furthermore, Hendrikx et al. (2016) noted
that measures of population health differ and result in various means of implementation
based on regional social needs. Moreover, Kindig and Isham (2014) indicated that
improving population health requires the collaboration of numerous organizations to
address the multiple social and physical determinants of health, and a single organization
cannot accomplish population health. Miranda et al. (2013) noted that health care
industries lack the analytical tools to support population management. Similarly, Phillips
et al. (2015) indicated that deficient data exchange at the level where patients access care
has an adverse influence on the capacity to achieve population health. George and
Shocksnider (2014) indicated nurse leaders require financial knowledge and access to key
business drivers to gain support for care coordination programs aimed at population
health.
Harder, Krulewitz, Jones, Wasserman, and Shaw (2016) indicated measuring
patient experience is a critical component when transforming the structure of the health
care system. Cook et al. (2015) described the patient experience as the patient’s

17
perception of care. Similarly, Bernabeo and Holmboe (2013) noted that patient
engagement and shared decision-making is a key system-level competency required to
achieve TAM objectives. Hibbard and Greene (2013) indicated that increasing patient
engagement improves the perceived patient experience. Hacker and Walker (2013) added
that the influence on patient experience is essential because patient behaviors account for
60% of health outcomes. According to Cook et al. (2015), improving health outcomes
involves utilizing patient experience feedback to guide patient engagement and quality
initiatives.
Hacker and Walker (2013) indicated that the accountable care organization
(ACO) and the patient-centered medical home (PCMH) are key concepts to
implementing TAM. The PCMH is a transformative concept of care aimed at re-
engineering the primary care practice (Jackson et al., 2013). The core tenets of the PCMH
include (a) team-driven care, (b) holistic care for the patient, (c) care coordination across
the continuum of care, (d) innovative methods of communication to improve access, and
(e) systematic approach to quality and safety (Jackson et al., 2013). According to Hahn,
Gonzalez, Etz, and Crabtree (2014), the National Committee for Quality Assurance
introduced the PCMH model to improve the quality of care within a primary care setting.
Health care organizations, however, may pursue the PCMH recognition as a label versus
a transformative process to improve the quality of care (Hahn et al., 2014). Similarly,
Howard et al. (2016) indicated that the pursuit of a PCMH extends beyond the verbiage
used to describe the practice to include the actions that support a transformation in the
culture of the organization.

18
The ACO is an ACA concept to transform the health care delivery system to meet
TAM objectives (Sandberg et al., 2014). In an ACO, there is a consortium of providers
contracted to reduce cost by creating a systematic, quality-based approach to managing a
population (Auerbach, Liu, Hussey, Lau, & Mehrotra, 2013). According to Kelleher et al.
(2015), the ACO success is in the ability to reduce cost and improve quality, thereby
improving the value of care. However, Rose, Zaslavsky, and McWilliams (2016) pointed
out that an ACO retaining a fee-for-service payment methodology for physicians and
specialists can cause conflicting priorities with volume versus value. Moreover, the
drivers of the ACO framework are the state and federal financial incentives for achieving
reductions in health care costs (Pham, Cohen, & Conway, 2014). Colla et al. (2014)
pointed out that the ACO framework allows for cost savings based on evidence-based
practice versus indiscriminate reductions in services.
Golden (2015) indicated there are more than 700 ACOs that provide health care
for an estimated 23 million people. According to Berkowitz and Pahira (2014), the core
elements of ACO development are as follows: leadership, governance, information
technology, analytical capacity, population health management, and care coordination.
Similarly, Hofler and Ortiz (2016) indicated that the two defining goals for an ACO are
enhancing the quality of care for a defined population and improving care coordination to
reduce the costs associated with hospitalizations and emergency room visits. However,
Golden indicated that policymakers will not realize the estimated $5 billion dollar saving
by 2019.
Corporate social responsibility theory. According to Carroll (2015), Bowen

19
initiated the CSRT body of literature to discuss the relationship between business and
society. Queen (2015) added that CSRT is an organization’s determination of the cost-
benefit of social initiatives. According to Husted et al. (2016), organizations grounded in
CSRT influence local communities by improving social benefits and decreasing social
problems. Scholars of the CSRT define the instrumental value of CSRT as the view of
societal issues based on the benefit to people (Husted et al., 2016). Theorists of CSRT
indicate the benefit of organizations engaging in socially responsible activities is a
positive reputation (Chernev & Blair, 2015). Additionally, Korschun, Bhattacharya, and
Swain (2016) pointed out that communicating CSRT initiatives to customers and
employees supports a high-performing work environment and positive reputation. There
is an economic value of maximizing on short- and long-term returns based on positive
public images (Tang, Gallagher, & Bie, 2015). Cheng, Ioannou, and Serafeim (2014)
posited that performance of CSRT philosophies affects business investments by lowering
capital constraints that could reduce the capacity to engage in strategic projects.
Likewise, Korschun et al. (2016) indicated that there are greater returns for organizations
with high CSRT activities. However, the CSRT was not the appropriate conceptual
framework for this study due to the emphasis on the social drivers of decision-making.
TAM was the most suitable framework based on the interrelated social and business
objectives driving systemic health care changes.
Corporate sustainability theory. In 1987, the World Commission on
Environment and Development introduced the CST to address environmental and social
problems that will impact future generations (Linnenluecke, Verreynne, Scheepers, &

20
Venter, 2017). Rego, Cunha, and Polónia (2015) posited that the definition of corporate
sustainability is diverse, resulting in the varied application of practice and theory.
Furthermore, Lozano (2015) indicated the organization’s leaders are the driving force for
implementing CST practices. The focus of corporate sustainability is on an organization’s
ability to meet the needs of internal and external stakeholders while maintaining
consideration for future stakeholder needs (Montiel & Delgado-Ceballos, 2014).
Similarly, Milne and Gray (2013) defined sustainability as a general concept about
consumption of natural resources and the impact of the consumption on future
generations. Hahn, Figge, Aragon-Correa, and Sharma (2015) noted a deficiency in
defining how organizations lessen the impact of activities on ecological systems.
Additionally, Milne and Gray stated the ecological component of the concept is
inconsistent among organizations, and business leaders debate the defining criteria for the
ecological contribution to society. Similarly, Whiteman, Walker, and Perego (2013)
indicated that scholars of the CST failed to provide a detailed account of how
organizations can operationalize CST interventions. The concept of sustainable
development is a blend of social, economic, justice, environmental, business, politics, and
legal activities to maintain future resources (Hahn, Pinkse, Preuss, & Figge, 2015). Hahn,
Figge, et al. (2015) noted that sustainable development is the fundamental principle
guiding CST.
Hahn, Pinkse, et al. (2015) describe the business implications for CST as a profit-
based strategic plan to address environmental and social pressures. Similarly, Eccles et al.
(2014) posited that there is a positive impact on the bottom line through economic

21
sustainability occurring in concert with ecological and social aspects of the business.
Moreover, the business considerations for CST require the integration of environmental
influences with the social and econimic factors (Whiteman et al., 2013). CST involves the
organization’s role in managing the ecological factors, social considerations, and external
perceptions (Eccles et al., 2014).
Hahn, Figge, et al. (2015) indicated the business considerations include the
potential for positive returns when investing in environmental and socially driven
initiatives. In this study, I did not focus on the ecological impact of business decisions on
future generations. Therefore, the CST was not the appropriate framework for this study.
TAM defines the objectives for systematic health care changes by implementing the
social and business tenets of improved population health, reducing per capita costs, and
improving the patient experience (Bodenheimer & Sinsky, 2014). Thus, TAM was the
more appropriate framework to study strategies health care leaders use to influence
decision making for care coordination program implementation.
Shareholder and stakeholder theory. Organizations grounded in shareholder
theory indicate the organization’s societal obligation is to maintain profitability for its
shareholders (Eccles et al., 2014). The morality of shareholder view is the right to
freedom of choice and ownership of personal property, without a violation of that right
for others (Mansell, 2013). In contrast, Friedman (1962) argued that only the individual
could possess social responsibility, not an organizational structure (Mansell, 2013).
Shareholders are owners that have the right to determine resource allocation (Mansell,
2013). The critique of the shareholder view is that resource allocation grounded in

22
maximizing owner profits is to the detriment of charity, employee morale efforts, and
other stakeholders (Queen, 2015). According to Mansell (2013), managerial staff is
contractually obligated to act based on the interests of the shareowners.
The stakeholder view expands the corporate relationship to multiple stakeholders
(Queen, 2015). Moreover, Kull, Mena, and Korschun (2016) posited that the outcome of
an organization depends on multiple stakeholder relationships. Critics hold that a focus
on broad stakeholder initiatives consumes managerial time in negotiations (Queen, 2015).
However, Kull et al. indicated that mutual trust developed with stakeholders provides a
competitive advantage. The critique of the stakeholder theory is the conflicting priorities
for managers to align with the separate agendas of owners versus stakeholders (Queen,
2015).
The stakeholder and shareholder theory are not mutually exclusive concepts, and
a balance between stakeholder costs and shareholder benefit is optimal (Queen, 2015).
Therefore, as individual conceptual frameworks, the stakeholder theory and shareholder
theory were not appropriate for this study. TAM was most suitable for this study to
determine how leaders make decisions that may influence social and business objectives
of health care.
Managed Care Organization for the Older Adult
The federal government contracts with risk-based managed care organizations to
provide services to federal health care beneficiaries (Newhouse & McGuire, 2014).
Newhouse and McGuire (2014) indicated that the intent of the managed care organization
for the older adult was to reduce costs and provide federal beneficiaries with an option

23
beyond federally sponsored health care. Twenty-seven percent of recipients of federally
sponsored health care enroll in one of the 3,300 managed care plans (Hellander et al.,
2013). MCOOA have the capacity to offer competitive benefit packages and care
coordination for beneficiaries (Landon et al., 2015). MCOOA receive a higher federal
reimbursement than traditional fee for service programs; however, the increase in
spending is not equivalent to a rise in quality (Hellander et al., 2013). Managed care plans
receive approximately $10, 123 per enrollee, which estimates to $136.2 billion a year
(Hellander et al., 2013).
Although the intent of MCOOA is to control health care expenditures, the federal
government spends $282.6 billion more for MCOOA than traditional fee for service
programs (Hellander et al., 2013). Baicker, Chernew, and Robbins (2013) pointed to a
shorter length of stay and reduction in hospital costs counterbalancing the additional
payments to MCOOA. Landon et al. (2015) support the assumption by indicating
MCOOA have lower utilization than the traditional federal health care program due to
network contracting and care management program implementation.
The federal government used the Star Rating system to determine MCOOA
performance based on the quality of care provided (Xu, Burgess, Cabral, Soria-Saucedo
& Kazis, 2015). Moreover, Reid et al. (2013) revealed the Star Ratings affect beneficiary
enrollment decisions; thus, influencing the MCOOA total enrollment and revenue. The
Star Ratings reflect Healthcare Effectiveness Data and Information Set (HEDIS)
measures, Consumer Assessment of Healthcare Providers and Systems surveys
(CAHPS), Health of Seniors surveys (HOS), and administrative data (Reid et al., 2013).

24
The provisions of the ACA reduced the higher payments to MCOOA and linked
payments to the quality of care through Star ratings (Xu et al., 2015). Landon et al.
(2015) stated the MCOOA could provide better quality than traditional federally
sponsored health care programs based on the use of flexible benefits and vast networks of
providers. The traditional federally sponsored health care program consists of benefits
determined by legislation and standard fee schedules (Baicker et al., 2013). According to
Reid et al. (2013), the Star Rating system is an essential business driver for MCOOA
because the federal government linked Star Ratings to the MCOOA’s financial
reimbursement in 2011. Additionally, state officials can enact quality payment withholds
based on the quality performance measures selected by the state (Morley et al., 2013;
Zainulbhai, et al., 2014).
The Obama Administration enactment of the PPACA modified the payment
structure of MCOOA requiring changes in business practices to ensure financial solvency
(Rak & Coffin, 2013). Moreover, the ACA changes in the health care reimbursement
structure include bonus payments and an increased capacity to enroll new members (Xu
et al., 2015). The current payment structure is that MCOOA receives capitated risk-
adjusted reimbursement from the federal government per enrollee for a given period
(Craver et al., 2016). According to Brown, Duggan, Kuziemko, and Woolston (2014), the
capitated risk-adjusted methodology is critical in eliminating the incentive to overutilize
services in a fee for service model. Morley et al. (2013) indicated that policymakers
reduced payments to MCOOA through the Financial Alignment Initiative.
The ACA included provisions to control costs and quality activities by regulating

25
the medical loss ratio for MCOOA (Harrington, 2013). Hall (2014) indicated tracking
medical expenditures is a key performance measure of the ACA. Conversely, Harrington
(2013) indicated a decreased focused on medical cost control would allow leaders to
increase spending on quality-based, clinical services. However, Harrington indicated
there was a decrease in the willingness to invest in innovative strategies without
measurable results. Harrington noted that the medical loss ratio regulation ensures the
health plans attribute the appropriate percentage of premium revenue for the medical care
and activities to improve the quality of care. Furthermore, the medical loss ratio of 80%
to 85% established by the ACA requires MCOOA to provide a rebate to insurers when
premium payments exceed the cost of providing medical care and specific quality-based
activities (Harrington, 2013). Health care economists suggested the ACA has decreased
the rate of health care spending (Hall, 2014). Proponents argue the recession and existing
downward trends may account for the deceleration of health care expenditure (Hall,
2014). However, those supporting the medical loss ratio indicate it is a solution to the
lack of transparency causing increased administrative costs (Harrington, 2013).
Affordable Care Act
The core components of the ACA include increasing health care coverage and
redefining the health care system (Berwick, Feeley, & Loehrer, 2015). On March 23,
2010, President Obama enacted the ACA into law and increased the insured population
by an estimated 16 million by 2015 (Hamel, Blumenthal, Abrams, & Nuzum, 2015).
However, Sommers, Buchmueller, Decker, Carey, and Kronick (2013) indicated the goal
of the legislators was for the ACA provisions to increase the insured population by 30

26
million. According to Orentlicher (2014), the ACA changes improved the health
insurance market by eliminating high premiums and coverage denials based on
preexisting conditions. Conversely, Hamel et al. (2015) indicated that increasing health
care coverage occurred by allowing the selection of affordable coverage through a health
plan marketplace, through federally sponsored expansion of the state-funded health
insurance program, extending dependent health coverage, and prohibiting discrimination
due to pre-existing conditions. Orentlicher indicated expanding state health care coverage
extends coverage to those previously uninsured, but does not equate to universal
coverage or better health outcomes.
Redefining the health care system is a complex component of the ACA provisions
(Hamel et al., 2015). Public and private organizational leaders focused on the
development of new care structures to transform the health care system (Berwick et al.,
2015). According to Hamel et al. (2015), redefining the health care system includes
changes in the payment structure, delivery models, workforce, and degree of innovation
for sustainability. Mery, Majumder, Brown, and Dobrow (2017) indicated that achieving
the objectives of TAM is the measure of transformation in the health care delivery
system. Likewise, Whittington et al. (2015) noted that TAM framework became a
national model to implement the health care redesign strategic objectives of the ACA.
Hamel et al. pointed out that systematic transformation of the payment structure included
readmission penalties, pay for performance strategies, reducing hospital-acquired
conditions through incentive payments, and bundled payment structures. Likewise,
Franklin and Busis (2016) indicated that the ACA provisions include investments in

27
billion dollar grants for care coordination and payment models aimed at achieving the
objectives of TAM.
Hirsch et al. (2014) indicated that ACA legislators introduced the, the
Independent Payment Advisory Board (IPAB) and the Patient-Centered Outcomes
Research Institute (PCORI) as the accountable agencies for redesigning the health care
infrastructure. The objective of the IPAB administrators is cost containment (Hirsch et
al., 2014). The IPAB commissioners evaluate payment methodologies for the federal
health care program based on changes in the per capita costs thresholds (Hirsch et al.,
2014). Frank, Basch, and Selby (2014) indicated that the role of the PCORI
administrators is to fund research that represents the voice of the community and supports
providing research to support informed health care decision-making. Moreover, the
PCORI aims to increase evidenced based health decision by funding clinical research
(Hirsch et al., 2014). According to Jain and Shrank (2014), legislators introduced the
Innovation Center to develop programs to improve care, advance system integration,
provide preventative initiatives, and improve state-based programs. Moreover, the
Innovation Center administrators are responsible for the evaluation of ideas to improve
the quality of care and reduce health care costs (Jain & Shrank, 2014)
The ACA legislators introduced the Federal Coordinated Healthcare Office
(FCHO) to ensure the integration of federal and state programs. In addition, the Financial
Alignment Initiative of 2011 is one of the Innovation Center programs to integrate the
payment and delivery of health care for the dual-eligible population (Prina, 2016).
According to Craver et al. (2016), the aim of the Financial Alignment Initiative is to

28
develop cost effective care models to minimize cost shifting between federal and state
health care programs and to reduce the fragmented approach to care delivery for the dual-
eligible population. The Financial Alignment Initiative presents opportunities to augment
service delivery models (Craver et al., 2016). Effective April 2014, 10 states signed a
capitated financial alignment memorandum of understanding with the federal government
to provide care to dual-eligible beneficiaries (Verdier, Streeter, Chelminsky, &
Nysenbaum, 2014). Verdier et al. indicated that the state and federal government officials
reduced the reimbursement to MCOOA based on the amount of savings expected for the
year. Moreover, the Welfare and Institution Code noted that MCOOA expected to
achieve savings through managing utilization patterns versus reducing reimbursement to
providers (Cutler, Rich, & Yee, 2013).
Care Coordination
Collaborative health care is a process recognized as a strategy to achieving TAM
(Katon & Unützer, 2013). Desjardins (2015) indicated care coordination is the
organization of patient care activities amongst multiple providers aimed at appropriate
health care utilization. According to Morton et al. (2015), coordination of care is
important in avoiding duplication of services, consistently delivering evidenced-based
guidance and improving access to care. Similarly, Xing, Goehring, and Mancuso (2015)
indicated that poor coordination of care and access issues are key drivers of increased
health care costs.
Care coordination is an essential component to addressing TAM objectives by
structuring payment models to promote physician involvement in care coordination

29
(Moreo, Moreo, Urbano, Weeks, & Greene, 2014). According to Aronson, Bautista, and
Covinsky (2015), the adjustment to the payment structure for clinicians represents a cost
efficient, evidenced-based change to the health care system. Similarly, Shaw, Asomugha,
Conway, and Rein (2014) indicated that the ACA legislators promote the advent of
innovative strategies to improve care coordination to reduce health care cost. Moreover,
the ACA provisions include contracts and grant opportunities for care coordination at
various levels of the care continuum (Desjardins, 2015). The ACA changes included the
FCHO to facilitate research of care coordination programs aimed at reducing cost and
integrating services for dual population (Frank, 2013).
Care coordination programs differ in approach, settings, provider, and population
(Marek et al., 2014). The variation and customization in programs present a challenge for
health care leaders to define successful implementation (Schultz, Pineda, Lonhart,
Davies, & McDonald, 2013). Schultz et al. (2013) noted that the industry lacks
consistency in defining care coordination, developing evidenced based practice, and
measuring coordination of care. Hong, Siegel, and Ferris (2014) revealed successful care
management models included: (a) customization, (b) qualitative and quantitative methods
for member identification, (c) a primary focus on care coordination, (d) relationship
building with patients and providers, (e) interdisciplinary team based on needs, (f)
training for team members, and (g) use technology to improve care. Tricco et al. (2014)
added that targeted interventions should include modifications with proven success such
as changes in the team, case management, and self-management strategies. Care
coordination becomes of increasing importance with an aging population with chronic

30
illness and comorbidities (Daveson et al., 2014). Similarly, Xing et al. (2015) noted that
targeting the care coordination intervention for the high-risk population is an effective
strategy for improving health care outcomes.
The return on investment for care coordination programs may vary. A review of
primary care-based care coordination programs revealed little to no benefit in utilization
outcomes (Marek et al., 2014). Similarly, McWilliams and Schwartz (2017) indicated
that care coordination programs did not influence cost savings for health care
organizations based on the need to expand resources and to increase the use of services.
In contrast, Marek et al. (2014) posited that transitional care was an effective care
coordination program feature to reduce inpatient utilization costs. Murphy and Neven
(2014) indicated that care coordination program assessments lacked a standardized
method of evaluating cost. Moreover, Murphy and Neven indicated that cost-
effectiveness was a fundamental element for leaders to determine an efficient allocation
of resources. The measure of success across programs was the ability to reduce inpatient
utilization outcomes. Kates, Shield, Behrend, and Noyes (2015) indicated that inpatient
cost would increase from $129.1 billion in 2008 to $234.9 billion in 2019.
Dual-Eligible Population
According to Whittington et al. (2015), choosing a population to implement the
three dimensions of the Triple Aim is a core competency for health care transformation.
Rittenhouse et al. (2015) indicated that the older adult population would account for 19%
of the total population by 2030. Moreover, the dual population requires coordination to
integrate the financial and medical components of the federal and state health care

31
programs (Prindiville, 2013). The Duals Office ensures the dual-eligible beneficiary
receives integrated benefits (Justice & Holladay, 2013). In addition, the provisions of the
ACA created regulatory groups to monitor activities for the dual-eligible population
savings (Brown et al., 2012). Eggbeer et al. (2013) pointed out that the dual-eligible
population is increasing at a rate double that of single-program beneficiaries. In addition,
the dual population has a higher incidence of social issues influencing the ability to
access health benefits (Ortega, 2016). Zainulbhai et al. (2014) added that medical and
behavioral complexities complicate care for the dual-eligible. Joynt, Gawande, Orav, and
Jha (2013) indicated that 10% of the older adult population consumes 50% of the federal
health care resources. Moreover, Powers, Chaguturu, and Ferris (2015) revealed that care
coordination programs could improve quality of life and reduce health care expenditures.
Eggbeer et al. indicated the system of managed care is appropriate for dual-eligible
beneficiaries because of the following: 40% of the population is younger than 65, 75% of
the dual-eligible population has not experienced a hospital admission, and 87% of the
dual-eligible reside at home. However, the dual-eligible population presents a challenge
when coordinating care amongst multiple providers and services (Eggbeer et al., 2013).
Kennedy (2013) indicated the dual-eligible population is at risk for fragmented care due
to the coordination required between multiple programs with varied benefits, ID cards,
appeal and grievance processes, and documentation.
Jung, Trivedi, Grabowski, and Mor (2015) indicated the dual-eligible population
account for 15% of state-sponsored health care enrollment and 39% of the expenses.
Eggbeer et al. (2013) posited that care coordination programs for dual-eligible

32
beneficiaries cost between $150 and $195 per enrollee. However, Brown et al. (2012)
concluded that programs could cost no more than $125 to $150 to realize savings.
MCOOA must reduce hospitalizations for the dual-eligible beneficiary by 15 per 100
enrollees to realize net savings (Brown et al., 2012). Additionally, the dual-eligible
population has 25% more chronic conditions than single-program recipients (Segal,
Rollins, Hodges, & Roozeboom, 2014). Cleave et al. (2013) indicated multiple chronic
conditions cause 98% of the federal health care expense. Moreover, the high incidence of
medical, social, and mental health needs complicates care coordination for the dual
eligible population. (Zainulbhai et al., 2014). Eggbeer et al. proposed that coordinating
and integrating care for the dual-eligible could improve the quality of care and save $20
billion in expenditures.
The Coordinated Care Initiative (CCI) in California consists of participation from
8 counties: Alameda, Los Angeles, Riverside, San Bernardino, Orange, Santa Clara, San
Diego and San Mateo (Cutler et al., 2013). Cutler et al. (2013) indicated that the CCI is
limited to a 3-year demonstration project to determine the statewide implementation of
unified state and federal health care benefits. Statistics reflects that 76% of dual-eligible
beneficiaries are 65 and older, and 37% are people with disabilities (Cutler et al., 2013).
The total dual population is approximately 1 million in California, of which, 223,084 are
in the eastern county of Southern California (Cutler et al., 2013). There is a 200,000 cap
on enrollment in the county (Cuter et al., 2013).
Fifteen states received a $1 million grant for the development of care management
programs for beneficiaries enrolled in federal and state-sponsored health care programs

33
(Lindeblad, 2013). The purpose of a care management program is to reduce expenditures
for the federal government and improve health outcomes for the dual population
(Lindeblad, 2013). The dual-eligible rate of hospitalization is 26% compared to 20% for
the single-program beneficiaries (Segal et al., 2014). Although hospitalizations are
necessary to regain optimal functions, hospitalizations for conditions identified as an
outpatient service are potentially avoidable hospitalizations (Wysocki et al., 2014).
Zainulbhai et al. (2014) determined that 44% of the dual-eligible population require long
term support services to address co-occurring conditions and social issues. Wysocki et al.
(2014) indicated improved transitions and community services can reduce avoidable
hospitalizations for the duals. Wysocki et al. explained the interconnectivity of medical
and long-term care services requires payment reform to encourage providers to improve
coordination of care and transition of care. Nevertheless, Segal et al. (2014) indicated
26% of the hospitalizations for the dual population were potentially preventable.
Zainulbhai et al. (2014) indicated that new strategies developed through the federal
demonstration projects are necessary to improve the quality of care, enhance access, and
reduce administrative barriers for the dual-eligible population. However, Prindiville
(2013) voiced a concern related to consumer protections to avoid new strategies that limit
care for the vulnerable dual-eligible population.
Readmissions
Ouslander and Maslow (2012) indicated reducing preventable hospitalizations is a
key initiative in achieving the objectives of TAM. Similarly, Hitch et al. (2016) stated
that the capacity to control high readmission rates is where health care systems are

34
deficient in meeting TAM objectives. However, care coordination is a consistent theme in
reducing the costs associated with readmissions (Carter, Bryant-Lukosius, DiCenso,
Blythe, & Neville, 2014). Gohil et al. (2015) indicated that readmissions occur within one
year for approximately 30% of hospitalized patients. Moreover, Hitch et al. noted that 1
in 5 beneficiaries enrolled in the traditional federal health care program readmit to an
inpatient level of care, costing the federal program 26 billion dollars annually.
Readmission is one of the key indicators of quality health care delivery (Hao et al., 2016).
Hao et al. (2016) indicated that preventative measures for readmission include focusing
on high-risk factors, strategic prevention strategies, and timely interventions for
vulnerable populations. The readmission rate for beneficiaries enrolled in the traditional
federal health care program is 20% and cost an estimated $17 billion (Fischer et al.,
2014).
According to Vipperla et al. (2014), identifying the risk and reason for
readmissions can reduce health care costs. Jiang et al. (2016) posited that readmissions
are the result of lack of primary care incentive to reduce readmissions, fragmented health
care, and poor access to care. Gohil et al. (2015) indicated that social determinants such
as education and income level have a direct impact on the probability of readmission.
Moreover, Dharmarajan et al. (2013) indicated that readmissions occur from generalized
vulnerabilities post hospitalization that include new disabilities, nutritional deficits, sleep
disturbance, and new medications. According to Picker et al. (2015), there is not a
standard preventative method to deter readmission due to the complexity of identifying
patients with a high risk of readmission. Likewise, Kahlon et al. (2015) indicated that

35
researchers and clinicians are unsuccessful in developing an algorithm to predict
readmissions. However, Mittler et al. (2013) noted that improved care coordination
during the transition from the hospital to an alternative level of care can prevent
readmissions.
There is limited evidence-based literature to determine a particular methodology
for transitional care interventions or identification of populations at greatest risk of
readmission (Kripalani, Theobald, Anctil, & Vasilevskis, 2014). However, poor
communication at the point of transition endangers the lives of older adults (King et al.,
2013). The older adult is at greater risk for medication discrepancies at the point of care
transition related to chronic conditions, comorbidities, functional impairments, and
complex medication regimens (Coughlin, Waidmann, & Phadera, 2012). Kripalani et al.
revealed there are various complexities to identifying specific interventions that affect
readmission. Similarly, Johnson et al. (2013) reported the transitional care program
elements include scheduling follow-up care, educating on the disease condition, and
training on warning signs that could result in readmission. Feltner et al. (2014) indicated
the focus on transitional care interventions improve readmissions by preventing adverse
events related to poor care coordination. Moreover, McWilliams and Schwartz (2017)
proposed that transitional care strategies include information technology, staff trained for
transitional care, interventions delivered in a home environment, and action planning for
inpatient and outpatient settings.
Although readmission is a significant portion of health care costs, health care
leaders may debate the value of readmissions as an indicator of health care quality.

36
Additionally, Fischer et al. (2014) indicated there is a lack of evidence to support using
readmission rates to measure the quality of hospital care. With the same vein, Parina,
Chang, Rose, and Talamini (2015) indicated readmission is not an independent measure
of quality based on the weak correlation to mortality rates. Gulati (2013) discovered 28%
of readmission are based on individual behavioral factors; therefore, negating the use of
readmissions as an indicator of hospital performance. Gu et al. (2014) determined the
dual-eligible status of patients has an adverse impact on the readmission rates. Therefore,
hospitals with high dual populations will receive a disproportionate share of readmission
penalties (Gu et al., 2014).
Relationship to Previous Leadership Research
Leaders require education in cost-benefit analysis and developing models that can
measure quality and cost (George & Shocksnider, 2014). In addition, leaders strategically
plan the development of a business case to influence stakeholders to invest in new
initiatives (Harvard Business Press, 2011). In the health care environment, a business
case manages clinical and financial performance expectations and provides an analysis of
the resources required for implementation (Song, McAlearney, Robbins, & McCullough,
2011). Health care leaders struggle with creating a business case for care coordination
because the standard business model does not apply (Perry & Stevens, 2013). According
to Wilf-Miron et al. (2014), health care leaders have difficulty determining the cost and
savings associated with health care interventions to improve the quality of care. Perry and
Stevens (2013) stated the organization’s mission and drivers of profit margin are
considerations when creating a business case. Creating the business case is necessary to

37
establish the value add for the proposed new initiative or for requesting resources for
existing projects (Perry & Stevens, 2013). A business case provides documentation of the
cost and benefits of potential investments (Maes, van Grembergen, & de Haes, 2013).
The business case provides a critical, formalized document for evaluating the allocation
of resources. The content of the business case can include an investment description,
investment objectives, investment requirements, investment impact, investment risk,
investment assumptions, and investment governance.
Health care leaders may lack strategies to garner support for care coordination
programs for the dual-eligible population. In addition, leaders may lack strategies to
reflect the effectiveness of care coordination programs. Kripalani et al. (2014) concluded
there is a lack of evidence-based literature to support a particular method for leaders to
reflect the benefits of implementing care coordination interventions. In addition, Wilf-
Miron et al. (2014) indicated that there is a variation in the delivery of care coordination
programs limiting the ability to do a cost analysis of the effectiveness. Similarly,
Schuller, Kash, Edwardson, and Gamm (2013) indicated there is a gap in the literature
defining how health care leaders enact organizational change. According to Wilf-Miron
et al. , there is an abundance of research to support implementing quality initiatives based
on performance indicators; however, there is a gap in the literature for leaders to use
when reflecting the associated financial implications. Similarly, Marek et al. (2014)
revealed a deficiency in the literature to defining how leaders reflect the cost-
effectiveness of care coordination programs. Likewise, Wilf-Miron et al. pointed out the
need for additional research on how leaders present a business case for implementation of

38
programs designed to address care for the complex population. Hong et al. (2014) noted
that there is little evidence of the ability of care coordination programs to reduce net costs
and demonstrate cost savings. According to Teut and Linde (2013), case study design is
an effective approach to study a field where there is a deficiency of existing research.
Researchers may use qualitative strategies to extract information from leaders as
key informants. Kash, Spaulding, Johnson, and Gamm (2014) employed qualitative
strategies to research success factors used by health care leaders to implement change
initiatives. Kash et al. used an open-ended interview process to engage participants in
describing critical success factors and offered insight into the process of successful
change implementation. In addition, Schuller et al. (2013) used qualitative strategies to
explore factors that can enable or disable implementation of change initiatives amongst
health care leaders and managers. Schuller et al. identified the use of a case study design
to provide a deeper understanding of the factors for leaders to implement change
successfully. Additionally, Brown et al. (2012) gave an analysis of four care coordination
programs that produced neutral cost results for the federal health care program for the
older adult. Brown et al. pointed out the need for health care leaders to control the cost of
interventions to realize savings when developing new care coordination programs.
According to de Waal et al. (2013), health care executives require evidenced based
business strategies to support the use of scarce resources for quality improvement in
health care.
Health care leaders in the position of manager, director, or vice president may use
TAM framework to define transformational changes within the organizational structure.

39
Findley, Matos, Hicks, Chang, and Reich (2014) suggested TAM framework as a
measure for leaders to determine the successful integration of community health workers
into the care coordination team. Likewise, Ory et al. (2013) used TAM objectives for
leaders to define the success of implementation of a care coordination program designed
to support self-management of chronic conditions. Lucatorto, Watts, Kresevic, Burant,
and Carney (2016) used TAM as the framework to determine the impact of the advanced
practice registered nurses in the care coordination program. In this study, TAM is the
conceptual framework to explore the strategies health care leaders positioned in the role
of manager, director, or vice president use to increase the resource allocation for care
coordination programs within a managed care setting.
I used a systematic approach to reviewing relevant journal articles and scholarly
books to guide the literature review process. Moreover, I provided a comprehensive
review of the literature on TAM, MCOOA, the Affordable Care Act, dual-eligible
population, care coordination programs, and readmissions. The literature review supports
the use of the qualitative research method to explore the strategies health care leaders use
to improve corporate financial investment in care coordination programs that include
TAM objectives.
Transition
In Section 1, I provided the foundation of the study to support the exploratory,
single case study design. Additionally, the section included (a) the background of the
problem, (b) the problem statement, (c) the purpose statement, (d) nature of the study, (e)
research question, (f) interview questions, (g) conceptual framework, (h) operational

40
definitions, (i) assumptions, limitations, and delimitations, (j) significance of the study,
and (k) the literature review. Section 2 is the detailed underpinnings of the qualitative,
case study. The objective was to provide the reader with the case study protocol driving
the research process. Section 2 contains a detailed account of the research process and
includes (a) purpose of the research, (b) the role of the researcher, (c) eligibility criteria
for participants, (d) research methodology, (e) research design, (f) population and
sampling, (g) ethical research, (h) data collection instruments and technique, (i)data
organization and analysis, and (j) reliability and validity. To conclude in Section 3, I
discussed the research findings, recommendations, and reflections.

41
Section 2: The Project
Policymakers increased efforts to reduce state and federal health care
expenditures by improving care coordination for the dual-eligible population (Gimm et
al., 2016). The provisions of the ACA included opportunities to refine the delivery of
services for the dually eligible. The challenge is in the ability of health care leaders to
define the business strategies for new service models aimed at cost reduction (Song et al.,
2011). Wilf-Miron et al. (2014) indicated the health care industry is inept in the
development of strategies to support business initiatives. In Section 2, I describe the
research purpose and provide a detailed account of the processes governing the
framework of the study.
Purpose Statement
The purpose of this qualitative single-case study was to explore the strategies that
health care leaders use to improve corporate financial investment in care coordination
programs that include TAM objectives. The target population was health care leaders in
the role of vice president or higher from one health care organization with experience
implementing strategies to improve corporate financial investment for care coordination
programs that included TAM objectives. The geographical region was Southern
California. Health care executives may consider the data from this study as a contribution
to social change if recommendations improve the quality of care for the dual-eligible
population.

42
Role of the Researcher
As the researcher, my role was as the primary instrument for data collection.
According to Hanson et al. (2011), the qualitative researcher is the primary instrument of
study when collecting interview data. My relationship with the topic, participants, and
area of study was that of an inside researcher. The inside researcher is a member of the
organization of study (Greene, 2014). I chose the inside researcher role to have direct
participant access and for a comprehensive understanding of the case study site. Greene
(2014) noted that inside researchers benefit from knowledge of the environment,
familiarity with participants, and access.
As the vice president of medical management, I possessed the knowledge of TAM
principles, care coordination, and the managed care environment. In addition, I had an
increased understanding of the business problem guiding the central research question
and a direct, established working relationship with the participants. However, the
participants were not subordinates. I interviewed leaders with accountability for work
processes and allocation of resources. According to McDermid, Peters, Jackson, and Daly
(2014), the advantage of a researcher employed by the research site is the understanding
of the organization and preexisting relationship with the participants. Similarly, Blythe,
Wikles, Jackson, and Halcomb (2013) indicated that inside researchers have an increased
depth of understanding, access, and rapport.
The three guiding principles of ethical research identified in the Belmont Report
provided the ethical foundation for the study. The role of the researcher is to ensure
respect for persons, beneficence, and justice (McDermid et al., 2014). Researchers

43
preserve the respect of persons by communicating the voluntary nature of the study and
providing information for informed decision-making (McDermid et al., 2014). The
ethical considerations include obtaining informed consent, providing honest dialog
regarding the study, and ensuring privacy and confidentiality (McDermid et al., 2014;
Yin, 2014). In addition, researchers maintain beneficence by maximizing benefits and
reducing harm (McDermid et al., 2014). Seidman (2012) indicated informed consent
minimizes participant risks. I used the informed consent process to guide ethical research
practices. To protect the confidentiality of the participants and reduce harm, I provided
them with unique identifiers rather than using their names or initials.
As an inside researcher, my role in this study was to mitigate bias through the
preservation of reflexivity. I mitigated bias and preserved reflexivity by using an
interview protocol and avoiding leading questions in the interview process. Collins and
Cooper (2014) indicated reflexivity is the initial process to determine how the view of the
researcher may influence the research process and findings. Similarly, Blythe et al.
(2013) indicated reflexivity is essential for inside researchers to reduce subjectivity and
bias. I used an interview protocol to establish uniformity and avoid deviation in the line
of questioning between participants (Appendix A). According to Jacob and Furgerson
(2012), an interview protocol preserves the focus of the study and ensures consistency in
the verbal exchange of information.
Participants
According to Barratt, Choi, and Li (2011), the experience of participants is critical
in determining the practicality of the research findings. Song et al. (2011) used a case

44
study design with organizational leaders as the key informants to extract qualitative data.
Likewise, Nicol, Mohanna, and Cowpe (2014) extracted information from senior health
care leaders to determine their views on the skills of clinical leaders. Cohen et al. (2014)
interviewed health care leaders to explore their understanding of the subject. In the
current study, the participant selection criteria included health care leaders at the level of
a vice president or above who used strategies to improve corporate financial investment
in care coordination programs that included TAM objectives.
According to Greene (2014), an inside researcher has direct access to the
organization of study as a member of the organization. Likewise, McDermid et al. (2014)
indicated the inside researcher has access to the organization and an understanding of the
site. Blythe et al. (2013) added that an advantage of inside research is the ability to gain
access as a member of the community of study. I gained access to the organization as an
inside researcher. I sent the letter of cooperation (Appendix B) that included a brief
description of the study to the chief medical officer via e-mail and scheduled a meeting to
obtain the signed letter of cooperation. After gaining the support of the chief medical
officer, I e-mailed the potential participants the informed consent with a voting option to
signify an agreement or disagreement with participation. The e-mail contained my direct
e-mail and telephone contact for potential participant questions prior to giving consent.
The informed consent included a description of the study and the disclosure information
identified in the Belmont report.
The participants did not have a reporting relationship with me or any employee
who reports to me. The participants were health care leaders in the position of vice

45
president or above who make or influence decisions about work practices and resource
allocation within the organization. According to McDermid et al. (2014), a researcher
employed by the research site develops an understanding of the organization and
establishes a preexisting relationship with the participants. In addition, Greene (2014)
noted that inside researchers benefit from the familiarity with participants and access.
Likewise, Blythe et al. (2013) added that inside researchers take advantage of access,
rapport, and depth of understanding.
Research Method and Design
I used the qualitative case study design to explore strategies for health care
leaders to improve corporate financial investment in care coordination programs that
included the TAM. According Bradley, Curry, and Devers (2007), qualitative researchers
provide an understanding of the complexity and breadth of a phenomenon. The
organizational phenomenon was the strategic processes health care leaders engage in to
procure funding for care coordination programs for the dual-eligible population. Yin
(2014) posited that a case study design can expand knowledge of organizational
phenomena.
Research Method
Researchers apply a qualitative, quantitative, or mixed-methods approach based
on the line of inquiry grounding the study. Moustakas (1994) indicated qualitative
researchers seek to obtain meaning from the core of the human experience. Likewise,
Denzin and Lincoln (2011) indicated qualitative researchers take an account of the
participant’s perspective through observations and interviews. Qualitative research

46
methods are ideal for identifying concepts and understanding phenomena (Bradley et al.,
2007). According to Myers (2013), qualitative research methods are appropriate for
exploratory, in-depth research on a topic that has limited existing research. Moreover,
Myers indicated the qualitative method allows the researcher to reveal the context in
which leaders generate decisions. I chose the qualitative method to explore strategies for
health care leaders in the position of manager, director, or vice president to improve
corporate financial investment for care coordination programs that included TAM
objectives. I conducted face-to-face interviews at the case study site, free of experimental
controls. The purpose of conducting the semi-structured interviews was to gauge the
participants’ experience and perspectives related to increasing resource allocation.
Qualitative strategies were appropriate for this study because the method allowed for
exploration of the decision-making process of health care leaders from the perspective of
the participants.
Quantitative researchers use numerical data to test hypotheses (Yilmaz, 2013).
Hanson et al. (2011) indicated quantitative researchers count occurrences and test
hypotheses. Quantitative researchers disregard context to focus on statistical techniques
to generalize findings (Myers, 2013). Because I focused on contextual content rather than
statistical numbers to test hypotheses, the quantitative method was not appropriate.
Investigators use mixed methods when the complexity of the research renders one
method insufficient (Wisdom et al., 2012). According to Yin (2014), researchers employ
mixed methods to address diverse research questions and to strengthen the data collected.
Likewise, Palinkas et al. (2015) indicated researchers use mixed methods to explore a

47
research topic using qualitative methods and to test a hypothesis using quantitative
methods. The qualitative method was appropriate for this study to extract the
participant’s insights and answer the central research question.
Research Design
The research designs prevalent in the literature include ethnography,
phenomenology, and case study (Hays & Wood, 2011). Additionally, Barratt et al. (2011)
indicated that researchers using the case study design to explore a phenomenon within the
bounds of the case. Moreover, the researcher using a case study design outlines the
questions and problems before conducting the study (Halaweh, 2012). Yin (2014)
described three conditions for choosing case study methods: research questions that use
how or why questions to explore operational connections, an environment free of
behavioral control, and the use of current events. I constructed the research question to
address an operational understanding of how health care leaders in the position of
manager, director, or vice president within a managed care environment gain funding for
care coordination programs. Research within a real-world context bounded by the
managed care site supported the application of a case study design. Researchers using an
ethnographic design focus on the culture of a group (Wolcott, 1999). Additionally,
Hanson et al. (2011) indicated ethnography requires the researcher to interact with
participants over an extended period in a setting where participants live. Moreover, in
ethnography the researcher uses participant observations and develops ongoing
relationships with the participants within a cultural framework (Watson, 2012). The
ethnographic design was not suitable because the study did not occur over an extended

48
period to gain knowledge of a culture. I did not employ extended periods of participant
observations as a data collection method, and I did not seek to develop continuous
relationships with the participants.
Phenomenological researchers aim to understand the lived or perceived
experiences of research participants (Tuohy, Cooney, Dowling, Murphy, & Sixsmith,
2013). Hays and Woods (2011) indicated phenomenological researchers aim to extract
meaning from understanding the individual’s conscious thoughts about a phenomenon.
Moreover, Moustakas (1994) reported that phenomenological researchers approach the
study of a phenomenon naively and without supposition. In this study, the focus was on
the strategies employed by health care leaders to gain financial support rather than the
subjective lived experiences of the participants. Therefore, the phenomenological design
was not appropriate.
Hanson et al. (2011) indicated qualitative researchers collect and analyze data
simultaneously to determine the point of saturation. According to Marshall, Cardon,
Poddar, and Fontenot, (2013), saturation occurs when there is a lack of new information
from the analysis of the interview data. Researchers achieve data saturation when there
are consistent themes noted in the data analysis process (Burda, van den Akker, van der
Horst, Lemmens, & Knottnerus, 2016). I achieved data saturation by interviewing
participants until there were no new themes identified in the analysis.
Population and Sampling
The purposeful sampling method supports the selection of information-rich cases
(Palinkas et al., 2015). Duan, Bhaumik, Palinkas, and Hoagwood (2015) indicated that

49
purposeful sampling is beneficial in capitalizing on scarce resources by identifying
participants who can provide information to support the purpose of the study. Nicol et al.
(2014) used purposeful sampling to gain insight from leaders involved in the key
leadership agenda. Kash et al. (2014) conducted a qualitative single case study using
purposeful sampling to extract the perceptions of health care leaders on evidence-based
leadership. Likewise, Cohen et al. (2014) implemented purposeful sampling to gain
information from health care leaders implementing population health strategies. I used
purposeful sampling to identify the participants in this study. The participant selection
criteria included health care leaders at the level of vice president or above who used
strategies to improve corporate financial investment in care coordination programs. The
sample size for the study was a minimum of six participants. Kelly (2010) noted that a
sample size of six to 10 participants could be appropriate for qualitative research.
Similarly, Barratt et al. (2011) indicated a sample of four to 10 is appropriate to capture
the essence of the phenomenon. Robinson (2013) indicated an estimated three to 16
interviews is appropriate in qualitative research. However, there is no predetermined
sample size for qualitative research methods (O’Reilly & Parker, 2013). Kelly posited
that the depth of information determines the sample size for a qualitative study as
opposed to a number based on a statistical calculation. Holloway and Wheeler (2013)
indicated a large sample size is uncommon and can jeopardize the depth and specificity
of qualitative research. Furthermore, the lack of new data determine the sample size
(Marshall et al., 2013). I selected a sample size of six participants to gain the depth of
information within a defined case study site. Data saturation occurs when no new

50
information emerges from the data analysis (O’Reilly & Parker, 2013). Marshall et al.
(2013) indicated data saturation is the point when the data extracted become redundant.
According to Burda et al. (2016), data saturation occurs when no new data emerge during
data collection and analysis. I completed parallel processes of conducting interviews and
analyzing the interview data to determine the point of saturation.
The participant selection criteria included health care leaders at the level of a vice
president or above who used strategies to improve corporate financial investment in care
coordination programs that included TAM objectives. The individual participant
interviews occurred in a closed environment to reduce interruptions, ensure privacy,
confidentiality, and accuracy of recordings. Moreover, I conducted the interview in a
closed environment onsite based on the preference of the participant. Consideration of the
actual setting is an essential step in the process of conducting interviews (Rabionet,
2011). According to Doody and Noonan (2013), an interview site without interruptions is
integral to the data collection process. Furthermore, Kelly (2010) indicated the interview
setting should be a mutually agreed upon location that is convenient for the participant.
Ethical Research
According to Seidman (2012), informed consent is the grounding principle of
ethically based research practices. The participants received and return the informed
consent form via email. I emailed the potential participants the informed consent with the
voting option to elect either an agreement or disagreement with participation in the study.
The email contained my direct email and telephone contact for participant questions prior
to the giving consent. Schrems (2014) indicated that researchers use the informed consent

51
process to provide the participant information to make a determination on involvement
(Schrems, 2014). Likewise, Wright (2012) indicated informed consent protects the rights
of the participant and provides information on the research project. Seidman outlined the
components of informed consent: (a) the invitation and explanation of the research study,
(b) potential risks and benefits involved with participation, (c) rights of the participants,
(d) confidentiality and privacy protections, and (e) Institutional Review Board (IRB) and
researcher contact information.
To ensure compliance with ethical standards and principles, I aligned the
informed consent with the components identified by Seidman (2012). The first element of
the informed consent for this study included the invitation and details of the research
study to provide participants material to make an informed determination on
participation. There were no incentives offered to research participants. The next
component contained verbiage to indicate potential risks and benefits to participation in
the research study. The third component of the informed consent for this study included
the rights of the participants and the voluntary nature of the study, including the right to
withdraw at any point in the research process. Participants could withdraw via email at
any point in the study. In the privacy and confidentiality section, I documented the
process of de-identifying the organization, providing unique identifiers for participants,
storing research documents in a steel, fire resistant locked lateral file cabinet for 5 years
and storing electronic data in a password protected electronic database. The final section
of the informed consent included my contact information.

52
The primary tools for establishing ethical research practices are the values and
ethics of the researcher (Merriam, 2014). To ensure the ethical protection of participants,
I adhered to the principles guiding ethical research practices and obtained approval from
Walden University’s IRB before conducting the research study. Furthermore, Morse and
Coulehan (2015) indicated researchers protect participants by limiting information and
avoiding demographic data. Therefore, I did not use participants’ name, but a unique
identifier that consisted of an alphanumeric combination. The participant data excluded
the demographic data, department, and title of participants to maintain confidentiality.
Data Collection Instruments
I was the primary data collection instrument in the research study. Peredaryenko
and Krauss (2013) indicated that the researcher is the primary data collection instrument
in qualitative research. Likewise, Chan, Fung, and Chien (2013) noted qualitative
researchers are the primary instrument in data collection, data analysis, and the
interpretation of findings. Hanson et al. (2011) noted that qualitative researchers are the
primary instrument of the study, in that, the researcher takes note of verbal and nonverbal
communication during the interview process and explores emerging thoughts.
The semistructured interviews and company documents were the data collection
instruments for this study. The semistructured interview allows for flexibility in the order
of questions to ensure sufficient exploration of the research question (Rowley, 2012). The
flexibility applied to semistructured interviews enables the researcher to engage the
participant to elicit a complete response (Saleem et al., 2014). Furthermore, researchers
using semistructured interviews can guide the participant through the participant’s

53
experience (Kelly, 2010). The next data collection instrument was company documents.
The documentary evidence will consist of minutes from managed care meetings, financial
performance meetings, business operations meetings, utilization management meetings,
and strategic planning meetings. Yin (2014) indicated document evidence can
substantiate or expand on other lines of evidence in the case study design. Myer (2013)
indicated meeting minutes from the organization of study provides documents relevant to
the research topic. Moreover, Ritchie, Lewis, Nicholls, and Ormston (2013) noted that
meeting minutes are pre-existing documentary evidence that will have pre-established
topic-based sorting to support data analysis.
I used an interview protocol as a guide to provide uniformity when conducting the
interview (Appendix A). Jacob and Furgerson (2012) indicated the interview protocol
describes the pre-interview statements, post-interview statements, and provides written
cues and prompts to remain on topic and ensure participants clearly define abbreviated
terms. According to Rowley (2012), the interview questions within the interview protocol
may contain 2 to 4 prompts to ensure sufficient response. Prompting within the interview
protocol allows the participant to expound on answers and provide the researcher with an
increased understanding (Doody & Noonan, 2013).
I included the interview protocol elements identified by Jacob and Furgerson
(2012). The pre-interview section of my interview protocol contained prompts for
establishing the appropriate setting for the interview, rapport building, informed consent,
and recording devices. The interview section of the protocol included scripting prompts
for an introduction to the research study. Moreover, the interview section included the

54
interview questions. I entered prompts to document verbal and non-verbal notes within
the interview protocol. Next, the interview protocol for this study included a post-
interview section to ensure participants received an explanation of subsequent
communication and my email contact information. The final section of the interview
protocol was the member check process. According to Jacob and Furgerson, researchers
use the interview protocol as a procedural guide when conducting the interview.
The interview protocol contained the member check section, which included the
interview questions, synthesized responses, verification of the accuracy of responses,
additional information from the participant, and a section for follow-up questions
(Appendix A). I used the member checking process to increase the reliability and validity
of the interview data. According to Burda et al. (2016), member checking can increase
the trustworthiness of the research by allowing participants to check for accuracy of the
researcher’s interpretations. Similarly, Harper and Cole (2012) pointed out that the
member checking process reduces errors in the data and the interpretation of the data.
According to Caretta (2015), member checking promotes mutual respect with participants
and preserves the authenticity of the research. After conducting the initial interviews, I
conducted the member check process by completing my transcript interpretations and
conducting second interviews to validate the responses. In addition, the participants will
receive a printed copy of the interview questions and my synthesized responses.
Data Collection Technique
I used a paper-based interview protocol to collect the interview data (Appendix
A). According to Jacob and Furgerson (2012), researchers use the interview protocol as a

55
procedural guide to collect interview data. Likewise, Rowley (2012) indicated that the
prompts within the interview protocol guide the researchers through the data collection
process. Doody and Noonan (2013) noted that the interview protocol supports the depth
of understanding by providing prompting to expand on interview questions. The
interview protocol contained the pre-interview, interview, post-interview, and member
checking sections (Appendix A).
The interviews occurred in a closed environment to promote privacy and
confidentiality. In addition, the participant received a unique identifier to maintain
confidentiality. I recorded each interview using a digital voice-recording device. The
participant received a written copy of the interview questions to provide a visual review
of the questions. I allowed a minimum of one hour for the interview and ample time for
the participant to answer each interview question, adhering to the protocol prompts and
time management. During the interview, I documented nonverbal cues on the interview
protocol and recorded post-interview thoughts for reflexive journaling. Additionally, the
participant received an explanation of subsequent interview requirements and my contact
information following the interview.
Yin (2014) indicates using multiple sources of evidence is an advantage of the
case study design. The main advantage of interview data is that interviewing allows the
participant to vocalize experiences (Rowley, 2012). Moreover, interviews allow the
researcher to increase the complexity of questions, probe for details, provide clarification
of questions, and ask open-ended questions about the emergence of data (Doody &
Noonan, 2013). Doody and Noonan (2013) indicated the disadvantage of collecting

56
interview data is that interviews are time-consuming and susceptible to bias due to the
participant’s desire to answer questions to appease the researcher. Similarly, Rowley
(2012) indicated the time constraints require researchers to collect data from a small
participant base reducing the generalization of the research findings.
The next data source included the collection of company documents. The
documents consisted of minutes from meetings relevant to the research topic. I developed
a list of meetings pertinent to the study based on past meeting minutes. In addition, I
reviewed relevant data extracted from meeting minutes during the interview to allow
participants the opportunity to expand on the company documents. The document data
consisted of paper documents and online documents.
Documents as an additional source of data are advantageous and allow for an
economical and accessible means of discovering emerging themes (Merriam, 2014). In
addition, documentary evidence serves as a means of validating data retrieved from other
sources (Yin, 2014). Ritchie et al. (2013) indicated documentary evidence allows for ease
of sorting by topic. However, Merriam (2014) indicated a limitation of documents is the
potential for misalignment and difficulty in authentication. Ritchie et al. noted
documentary evidence potentially limit the application to research due to preexisting
purposes. Yin (2014) added that although documentary evidence is pertinent to the case
study design, author bias is a potential disadvantage.
Burda et al. (2016) noted that researchers use member checking to provide an
accurate account of the participant’s meaning. Likewise, Harper and Cole (2012)
indicated member checking is a means to reduce the probability of inaccurate data

57
interpretations. Moreover, member checking increases the credibility of the data by
having the participant validate the accuracy of the researcher’s interpretation (Caretta,
2015). I conducted an additional interview for the member checking process. The
participants received the interview questions and my synthesized responses to validate
the accuracy of the data interpretation. I audio recorded the interview and asked that the
participant clearly state if the interpretation is correct. In addition, the participant had
approximately one hour to provide additional information and to ask follow-up questions.
I clarified discrepancies identified and validated the accuracy of the changes during the
member check interview.
Data Organization Technique
In this study, the principal organization tool is the interview protocol. According
to Doody and Noonan (2013), researchers use the interview protocol to organize data for
the interview process to assist in extracting pertinent information from participants
(Doody & Noonan, 2013). Likewise, Jacob and Furgerson (2012) indicated that the
interview protocol is a procedural document that organizes the interview process and data
collected. In addition, researchers use an interview protocol to organize data in
preparation for the analytical phase of the research process (Rabionet, 2011).
As the primary instrument of the research study, the additional data organization
processes included reflexive journaling and a research log. Researchers use a reflexive
journaling to document preconceptions that may influence the research process (Tufford
& Newman, 2012). Furthermore, reflexive journaling documents the personal
experiences and beliefs of the researcher (Berger, 2015). According to Ward, Furber,

58
Tierney, and Swallow (2013), researchers use reflexive journaling to record ideas and
decision-making. I employed the use of reflexive journaling to document thoughts and
perceptions prior to and during the research process. According to Merriam (2014),
qualitative researchers use research logs to make note of obstacles and ideas stemming
from the data collected. Likewise, Yin (2014) indicated that researchers use notes to
document preliminary data interpretations. Ritchie et al. (2013) indicated that researchers
use a log to keep track of emerging analytical thoughts. I used a research log to document
emerging conclusions from the data. In addition, I labeled and categorize the research log
entries based on notes documented from interview and company documents. I stored the
data in a steel, fire resistant locked lateral file cabinet for 5 years.
Data Analysis
Yin (2014) identified multiple sources of evidence as a core principle of data
collection in the case study design. Therefore, I used methodological triangulation to
analyze data using multiple data collection methods. According to Hussein (2015),
triangulation entails analyzing the research question from multiple vantage points to
establish research validity. Moreover, triangulation is a strength in the application of a
case study design (Houghton, Casey, Shaw & Murphy, 2013). According to Carter et al.
(2014), researchers establish methodological triangulation by using multiple data
collection methods to research a phenomenon. Furthermore, Bekhet and Zauszniewski
(2012) indicated that methodological triangulation allows the researcher to explore the
phenomenon by using multiple qualitative strategies or multiple quantitative strategies,
not a combination of the two. The data collection techniques for methodological

59
triangulation included interview data and company documents. The documentary
evidence consisted of minutes from managed care meetings, financial performance
meetings, business operations meetings, utilization management meetings, and strategic
planning meetings.
Data analysis is the process of transforming data from the descriptive process to a
level of interpretation (Vaismoradi, Turunen, & Bondas, 2013). Moreover, researchers
separate text data and make logical connections to make inferences from raw data during
the data analysis phase (Wahyuni, 2012). Thematic analysis requires the researcher to
become familiar with data by transcribing, reviewing data multiple times, and noting
ideas (Vaismoradi et al., 2013). In addition, Bradley et al. (2007) indicated reviewing the
overall data without coding is the initial step in comprehending data. First, I reviewed the
data multiple times to familiarize myself with the information. Following the data review,
I employed the use of NVivo11 memo links to journal my thoughts and ideas.
I used NVivo11 as the software to guide the sequential process for data analysis
using coding, mind-mapping, and identification of themes. NVivo11 is the most
recognized Computer-Assisted Qualitative Data Analysis Software tool (Zamawe, 2015).
Houghton et al. (2013) supported the use of NVivo11 to analyze observation, interview,
and documentary evidence in a case study research design. In addition, Bernauer,
Lichtman, Jacobs and Robinson (2013) indicated that researchers could use NVivo11 to
support the critical thought processes involved in analyzing data. In addition, I used
NVivo11 to determine commonalities by linking the key themes from the data with the
conceptual framework, existing literature, and literature published after the proposal

60
approval date. According to Zamawe (2015), NVivo software can organize data based on
the purpose. In addition, Bernauer et al. (2013) indicated NVivo software aids in the
analysis process by organizing data based on themes and relationships. Moreover,
Houghton et al. noted NVivo is a data management tool that researchers use to provide a
comprehensive audit trail. First, I imported the text from the reflexive journal to the
source folder. Then, I organized the reflexive journaling according to the assigned
participant or assigned company document. I imported the company document files into
the source folder titled Company Documents. I labeled the company documents based on
the type of meeting. The meeting types included managed care meetings, financial
performance meetings, business operations meetings, utilization management meetings,
and strategic planning meetings. Next, I imported the audio files from the initial
interviews into the source folder titled Interviews. I listened to audio files and transcribed
the data within NVivo11. I added a node to assign the unique identifier to the participant
interview to capture the response by participant. I reviewed the transcriptions three times
prior to coding.
Yin (2014) indicated that the coding process is an essential phase of data
interpretation for qualitative research. Moreover, Elo et al. (2014) indicated that
qualitative researchers must code and interpret data using a structured approach.
Thematic analysis is a structured data analysis strategy of using codes, themes, and
theory (Bradley et al, 2007). I queried the data based on the 100 most frequent words
with four characters or more for open coding and thematic analysis. Bohren et al. (2014)
indicated that researchers use open coding to establish broad codes from the research

61
data. Likewise, Wolfswinkel, Furtsmueller, and Wilderom (2013) noted that researchers
apply open coding strategies to extract concepts from the data. Kolb (2012) posited that
researchers use open coding to identify different categories within the data. The analysis
process included the use of the NVivo11 coding stripes to provide documentation of the
coded sections of the interview and document data. The next process included the
NVivo11 tag cloud visual diagram feature to illustrate the themes based on the word
frequency for axial coding. Axial coding is the process of using the categories identified
in open coding to identify the main themes of a research study (Wolfswinkel, et al.,
2013). Kolb indicated that researchers use axial coding to establish connections between
the codes revealed during the open coding phase. Similarly, Bohren et al. (2014)
indicated that qualitative researchers use axial coding to separate data into themes. The
final step was to use the interview data and document data to create a visual chart of the
themes identified for methodological triangulation and selective coding. According to
Wolfswinkel et al. (2013), selective coding is the process of refining themes identified in
the axial coding phase. Likewise, Kolb indicated that researchers use selective coding to
further identify, connect, and validate core themes. King et al. (2013) noted that
researchers validate conclusions using selective coding to verify patterns. The data
collection and data analysis process occurred simultaneously to establish the point of data
saturation.

62
Reliability and Validity
Reliability
Dependability is the quality indicator used to establish reliability (Houghton et al.,
2013). The measure of quality in qualitative research depends on the documentation of
research processes, the analytical procedures, and the thought processes of the researcher
(Mertens, 2014). Dependability reflects the stability and accuracy of the research data
(Houghton et al., 2013). Furthermore, Thomas and Magilvy (2011) noted dependability
as the extent to which other researchers can follow the decision-making processes.
According to Houghton et al. (2013), NVivo11 software reflects the thematic
analysis process and provides an internal audit of findings. Although changes can occur
in the qualitative research method, researchers establish dependability by documenting
the changes for public auditing (Mertens, 2014). Moreover, researchers use a structured
audit trail to create dependability (Houghton et al., 2013). I provided a detailed account
of the research purpose, participants, research method, research design, population and
sampling, consents, data collection, data organization, and data analysis to establish
dependability and provide an audit trail. I used NVivo11 software to reflect the data
analysis and path of decisions used to reveal themes. Additionally, I documented in the
member checking section of the interview protocol the changes to participant responses
to provide an audit trail of the response verification process and establish dependability.
Validity
The specific quality indicators used to establish validity include creditability,
transferability, and confirmability (Wahyuni, 2012). Establishing credibility involves

63
processes that supports the researchers in ensuring interpretations are accurate and easily
recognized by those within the industry of study (Lohle & Terrell, 2014). I used
member checking of the interview responses to establish credibility. Member checking
increases credibility by allowing the participant to verify the accuracy of the researcher’s
interpretations of the interview data (Caretta, 2015). Likewise, Burda et al. (2016)
indicated researchers use member checking to ensure accurate conveyance of the
participant’s meaning. Additionally, Harper and Cole (2012) indicated member checking
is a means to reduce the likelihood of inaccurate data or erroneous data interpretations.
The member checking section of the interview protocol included the participant’s
validation of my synthesized responses. To further establish credibility, I used interviews
and company documents for methodological triangulation. The advantage of using
methodological triangulation is in the confirmation of research findings, the expansion of
data available for analysis, and the increased validity of the study (Bekhet &
Zauszniewski, 2012). Carter et al. (2014) indicated that researchers use methodological
triangulation to establish the credibility of findings by confirming findings between
sources of evidence. Likewise, Bekhet and Zauszniewski (2012) noted that
methodological triangulation augments validity and supports the confirmation of
findings. According to Hussein (2015), researchers use methodological triangulation to
improve credibility. I compared themes identified in the documentary data and the
interview data collected to discern methodological triangulation.
Black, Palombaro, and Dole (2013) indicated that investigators use transferability
to establish the trustworthiness of research. Moreover, transferability is the extent to

64
which the research findings of a research study can apply to different settings (Elo et al.,
2014). Houghton et al. (2013) indicated the overarching aim of establishing
transferability is for the reader to determine the applicability of research findings and
methods to different settings (Houghton et al., 2013). Moreover, Wahyuni (2012) noted
that researchers use detailed descriptions of the case study site to improve transferability
of research processes to other settings. Thomas and Magilvy (2011) specified that
researchers establish transferability by providing rich descriptions of the population. To
achieve transferability, I used a research log and provided thick descriptions of the
phenomenon, case study site, participant criteria, research processes, and findings to
allow readers to determine the applicability to different settings. In addition, I used an
interview protocol and ensured adherence to the data collection and data analysis
techniques for the case study design.
The predominant role of creating confirmability is to establish the reliability of
the findings by ensuring the findings do not represent the views of the researcher (Tong
& Dew, 2016). The confirmability process reduces bias by providing transparency
through reflexivity (Thomas & Magilvy, 2011). Furthermore, Wayhuni (2012) indicated
that confirmability allows others to confirm that research findings are an accurate
conveyance of participant views versus the opinion of the researcher. I used NVivo11
software to demonstrate confirmability through query searches to demonstrate findings
are beyond the investigator’s determination. According to Collins and Cooper (2014),
researchers use emotional reflexivity to reveal the predispositions of the researcher and to
reflect self-awareness. I documented preconceived thoughts using reflexive journaling.

65
Moreover, Thomas and Magilvy (2011) added that self-awareness of potential bias and
documenting preconceptions establishes trust and confirmability. Likewise, Houghton et
al. (2013) indicated documenting any personal thoughts or insights establishes reflexivity.
I used reflexive journaling following each interview to document personal thoughts or
feelings.
Data saturation occurs when no new concepts emerge from data analysis
(Marshall et al., 2013). According to O’Reilly and Parker (2013), data saturation
determines the adequacy of the sample selected. Data saturation is the point where
researchers note uniformity in codes and themes (Burda et al., 2016). Data saturation
occurred following the fifth interview. There was no new information emerging from the
interviews and company documents.
Transition and Summary
In Section 2, I presented the rich description of the research purpose and
processes. The section includes the role of the researcher, the participant selection
process, and justification for the population and sampling. Section 2 included a detailed
account of the ethical principles guiding the research. There is an expansion of the
rationale and scholarly justification for using the qualitative research method and case
study design. I included thick descriptions of the data collection instruments, data
collection techniques, data organization, and data analysis to support the external auditing
of processes. The final components of Section 2 consisted of the methods to achieve
reliability and validity through establishing dependability, creditability, transferability,

66
and confirmability. In Section 3, I included the research findings, recommendation for
action, and future research considerations.

67
Section 3: Application to Professional Practice and Implications for Change
Introduction
The purpose of this qualitative single case study was to explore the strategies that
health care leaders use to improve corporate financial investment in care coordination
programs that include TAM objectives. Section 3 consists of the (a) presentation of
findings, (b) application to professional practice, (c) implications for social change, (d)
recommendations for action, (e) recommendations for future research, and (f) reflections.
The data extracted from the semistructured interviews revealed the overall strategies to
garner support for care coordination programs. According to Wilf-Miron et al. (2014),
decision-makers expect leaders to present a return on investment for improvement in
health care. The health care leaders interviewed noted the importance of using data to
demonstrate a decrease in health care costs of care coordination programs. Health care
leaders also indicated that the structure of the care coordination program must align with
the organization’s strategic mission. Whittington et al. (2015) indicated that the success
of deploying the TAM depends on the integration of the key tenets with the
organizational structure. Participants in the current study also indicated that leaders must
focus on the high-needs, high-cost populations. Whittington et al. pointed out that health
care leaders must complete a population assessment to select populations in which the
three objectives of TAM apply. Finally, participants in the current study indicated that
leaders must work in partnership with primary care practices for interprofessional
collaborative practice.

68
Presentation of the Findings
The central research question for this study was as follows: What strategies can
health care leaders use to improve corporate financial investment in care coordination
programs that include the TAM objectives? I used semistructured interviews and archival
documents to collect data for this study. I analyzed the data using NVivo 11. The four
themes that emerged from my analysis included (a) reflecting a reduction in health care
cost, (b) focusing on high-need, high-cost populations, (c) partnering with primary care
practices, and (d) patient-centered care.
Theme 1: Reducing Health Care Costs
The key tenets of the TAM include reducing per capita health care costs,
improving patient experience, and providing population health (Bodenheimer & Sinsky,
2014). Although there are evidence-based care coordination methods that provide high
value, health care leaders lack the funding source for implementation (Rowe, Fulmer, &
Fried, 2016). The most common strategy to obtain financial support was indicating how
investing in care coordination programs can reduce the overall costs for the organization.
Six (100%) participants indicated that cost reduction is a critical strategy to improve
investment in care coordination programs. However, the specific cost reduction strategy
differed among participants. As depicted in Figure 1, participants with more than 20
years of experience recommended specific measures for cost reduction at a higher
frequency than participants with less experience. The data indicated that participants with
less than 20 years of experience referenced generalized cost savings with greater
frequency than participants with more than 20 years.
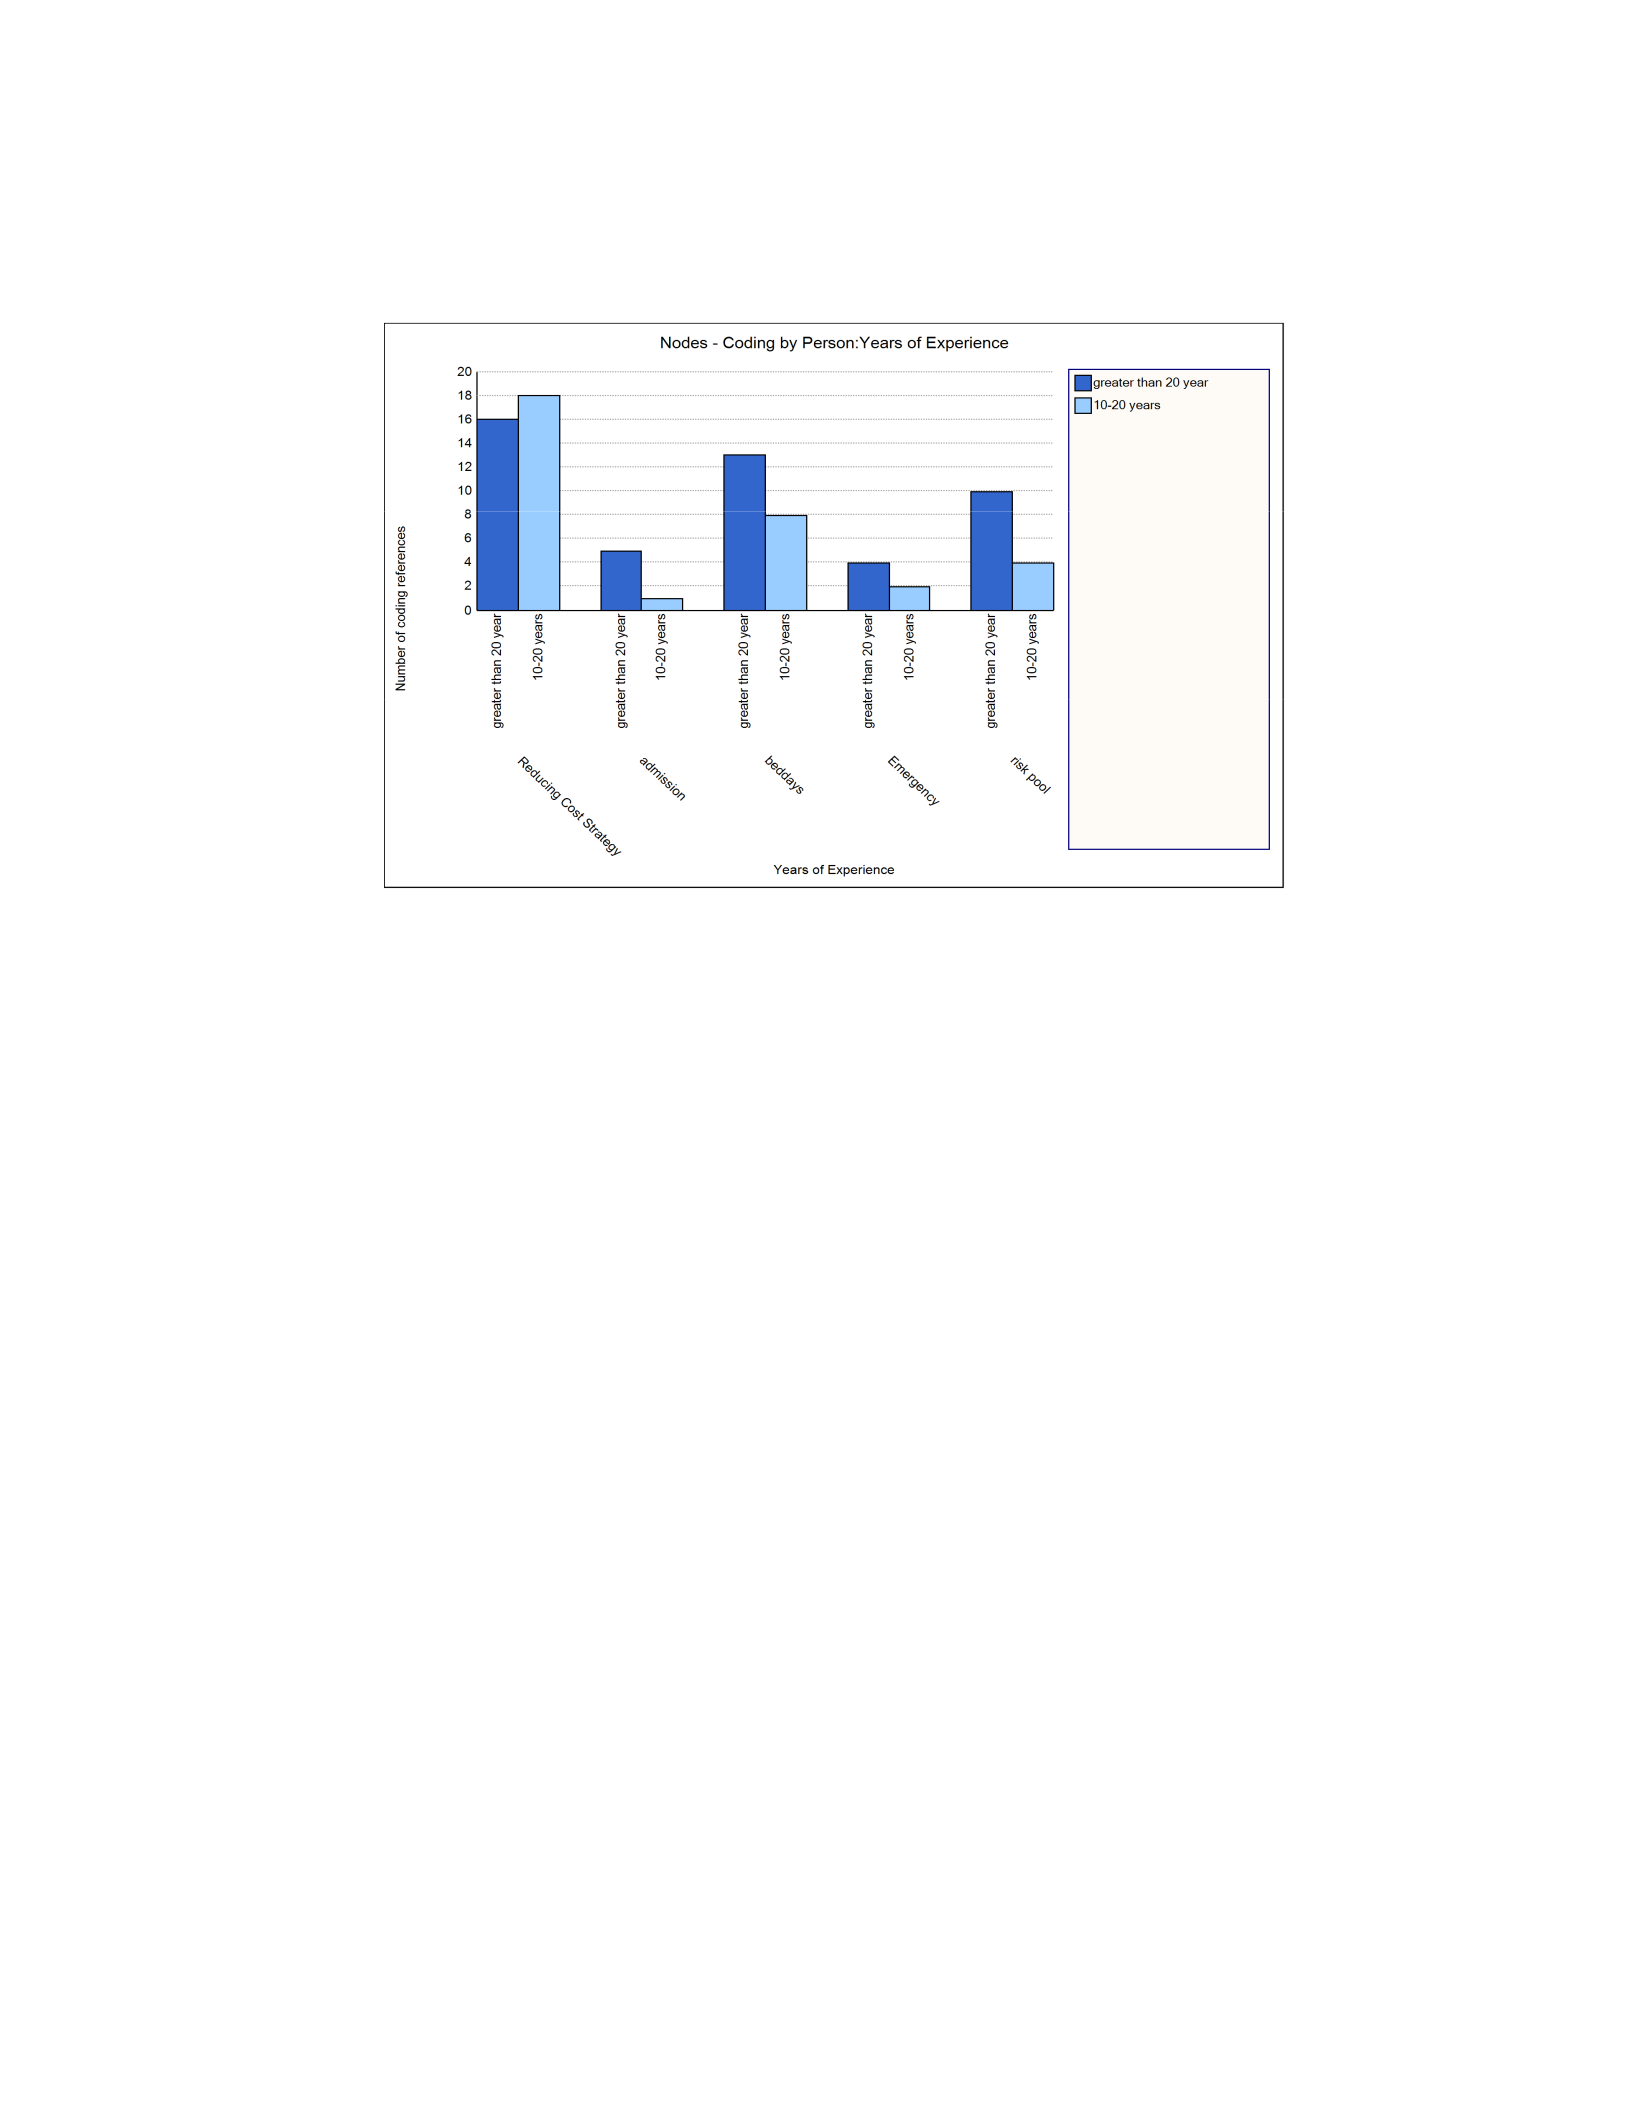
69
Figure 1. Cost reduction strategy coding by participant.
All participants indicated the capacity of the care coordination program to reflect
a cost saving is a critical strategy. Six (100%) participants identified hospital utilization
as a cost driver that warrants data analysis and strategic planning for the structure of care
coordination programs. According to Brown et al. (2012), MCOOA must reduce
hospitalizations by 15 per 100 participants to realize net savings. Likewise, Ouslander
and Maslow (2012) noted that reducing hospitalization is a key initiative in achieving the
TAM. One participant in the current study pointed out that leaders should resist the urge
to cite the TAM, but should clearly define the organizational measures that will affect the
TAM objectives. The specific hospital utilization data identified were bed days,
admissions, readmissions, emergency visits, and inpatient risk pool performance. All
participants in this study referenced bed days as a measure for consideration when
developing strategies for care coordination supports. Five (83%) participants referenced

70
inpatient risk pool data as an element to reflect the performance of a care coordination
program. Hitch et al. (2016) stated that controlling readmissions is a key element of
achieving the TAM objectives. Similarly, 67% of the participants in the current study
referenced readmissions as a key cost consideration. In the table below, I indicate the
frequency of principle metrics and the weighted percentages.
Table 2
Principle Metric Reference
Metric
Total number of references Weighted percentage
Risk pool performance 15 .95
Bed days 20 .90
Readmission 11 .50
Emergency visit 6 .27
Admissions 6 .27
Song et al. (2011) indicated that the business case for care coordination defines
the clinical and financial performance expectations for program implementation. Five
(83%) of the participants indicated that leaders should understand financial data from
health plan risk pools to use as a strategy to garner fiscal support. According to 33% of
the participants, leaders seeking to present a strong case for monetary support must use
financial trends to reflect gains versus depending solely on clinical benchmark metrics.
However, de Waal et al. (2013) revealed that health care leaders might not have the
competencies to develop a business case presentation to support the implementation of
new strategies. The participants in the current study revealed two strategies to address
gaps in competency. Four (67%) of the participants indicated that leaders could use
external consultants as a strategy to garner support and capture data on care coordination

71
practices within the industry. One (17%) of the participants noted that leaders could
capitalize on internal business units that focus on workforce strategic planning to provide
data on cost considerations and return on investment for program implementation.
McGinley and Gabbay (2016) identified the total cost per member per month as a
measure used to determine cost savings when transforming health care delivery models.
McWilliams and Schwartz (2017) pointed out that services and cost of care increase with
care coordination programs. Four (67%) of the participants in the current study identified
per member per month costs as a relative indicator to determine cost savings. One
participant indicated that per member per month data should be reflective of the financial
risk model of the MCOOA. According to 33% of the participants, executive leadership
understands the per member per month payment methodology, and health care leaders
should present cost analysis in a format familiar to the intended audience. Four (67%) of
the participants indicated that ensuring senior leadership understands the key metrics and
the managed care environment is a key strategy to garner financial support.
Theme 2: High-Need, High-Cost Population Focus
Blumenthal, Chernof, Fulmer, Lumpkin, and Selberg (2016) indicated that health
care leaders improve the system of health care by concentrating on the high-need, high-
cost (HNHC) population. Four participants (67%) in the current study noted that
strategies to garner support should include how health care leaders intend to influence the
HNHC population and reduce cost. Blumenthal et al. posited that the HNHC individuals
are 5% of the population and account for 50% of the expenditures. Four (67%) of my
participants concurred that there is a disproportionate share of the cost attributed to a

72
small population. In addition, the participants revealed that a focus on the HNHC patients
allows leaders to track and trend data to present the return on investment for a small
population. Care coordination programs that focus on the HNHC populations have the
capacity to meet the TAM objectives (Larson, Hoffman, & Artman, 2017). Four (66%) of
the current study participants reported that a successful business practice to garner
financial support and to address the overall TAM is to present strategies to address the
HNHC population, further confirming findings from the existing literature on HNHC
populations.
As shown in Figure 2, participants at the level of vice president with fewer than
20 years of experience referenced HNHC at a greater frequency than other participants.
All participants considered the dual-eligible population as a HNHC population. I
confirmed the findings related to the dual-eligible population reflecting a HNHC
population through recent literature. According to Ortega (2016), the dual-eligible
population has a higher incidence of chronic illness and higher costs. Similarly, Doyle,
Emmett, Crist, Robinson, and Grome (2016) indicated that the dual-eligible population
has a greater frequency of being poor, disabled, sick, and mentally ill compared to
beneficiaries of a single health care program.
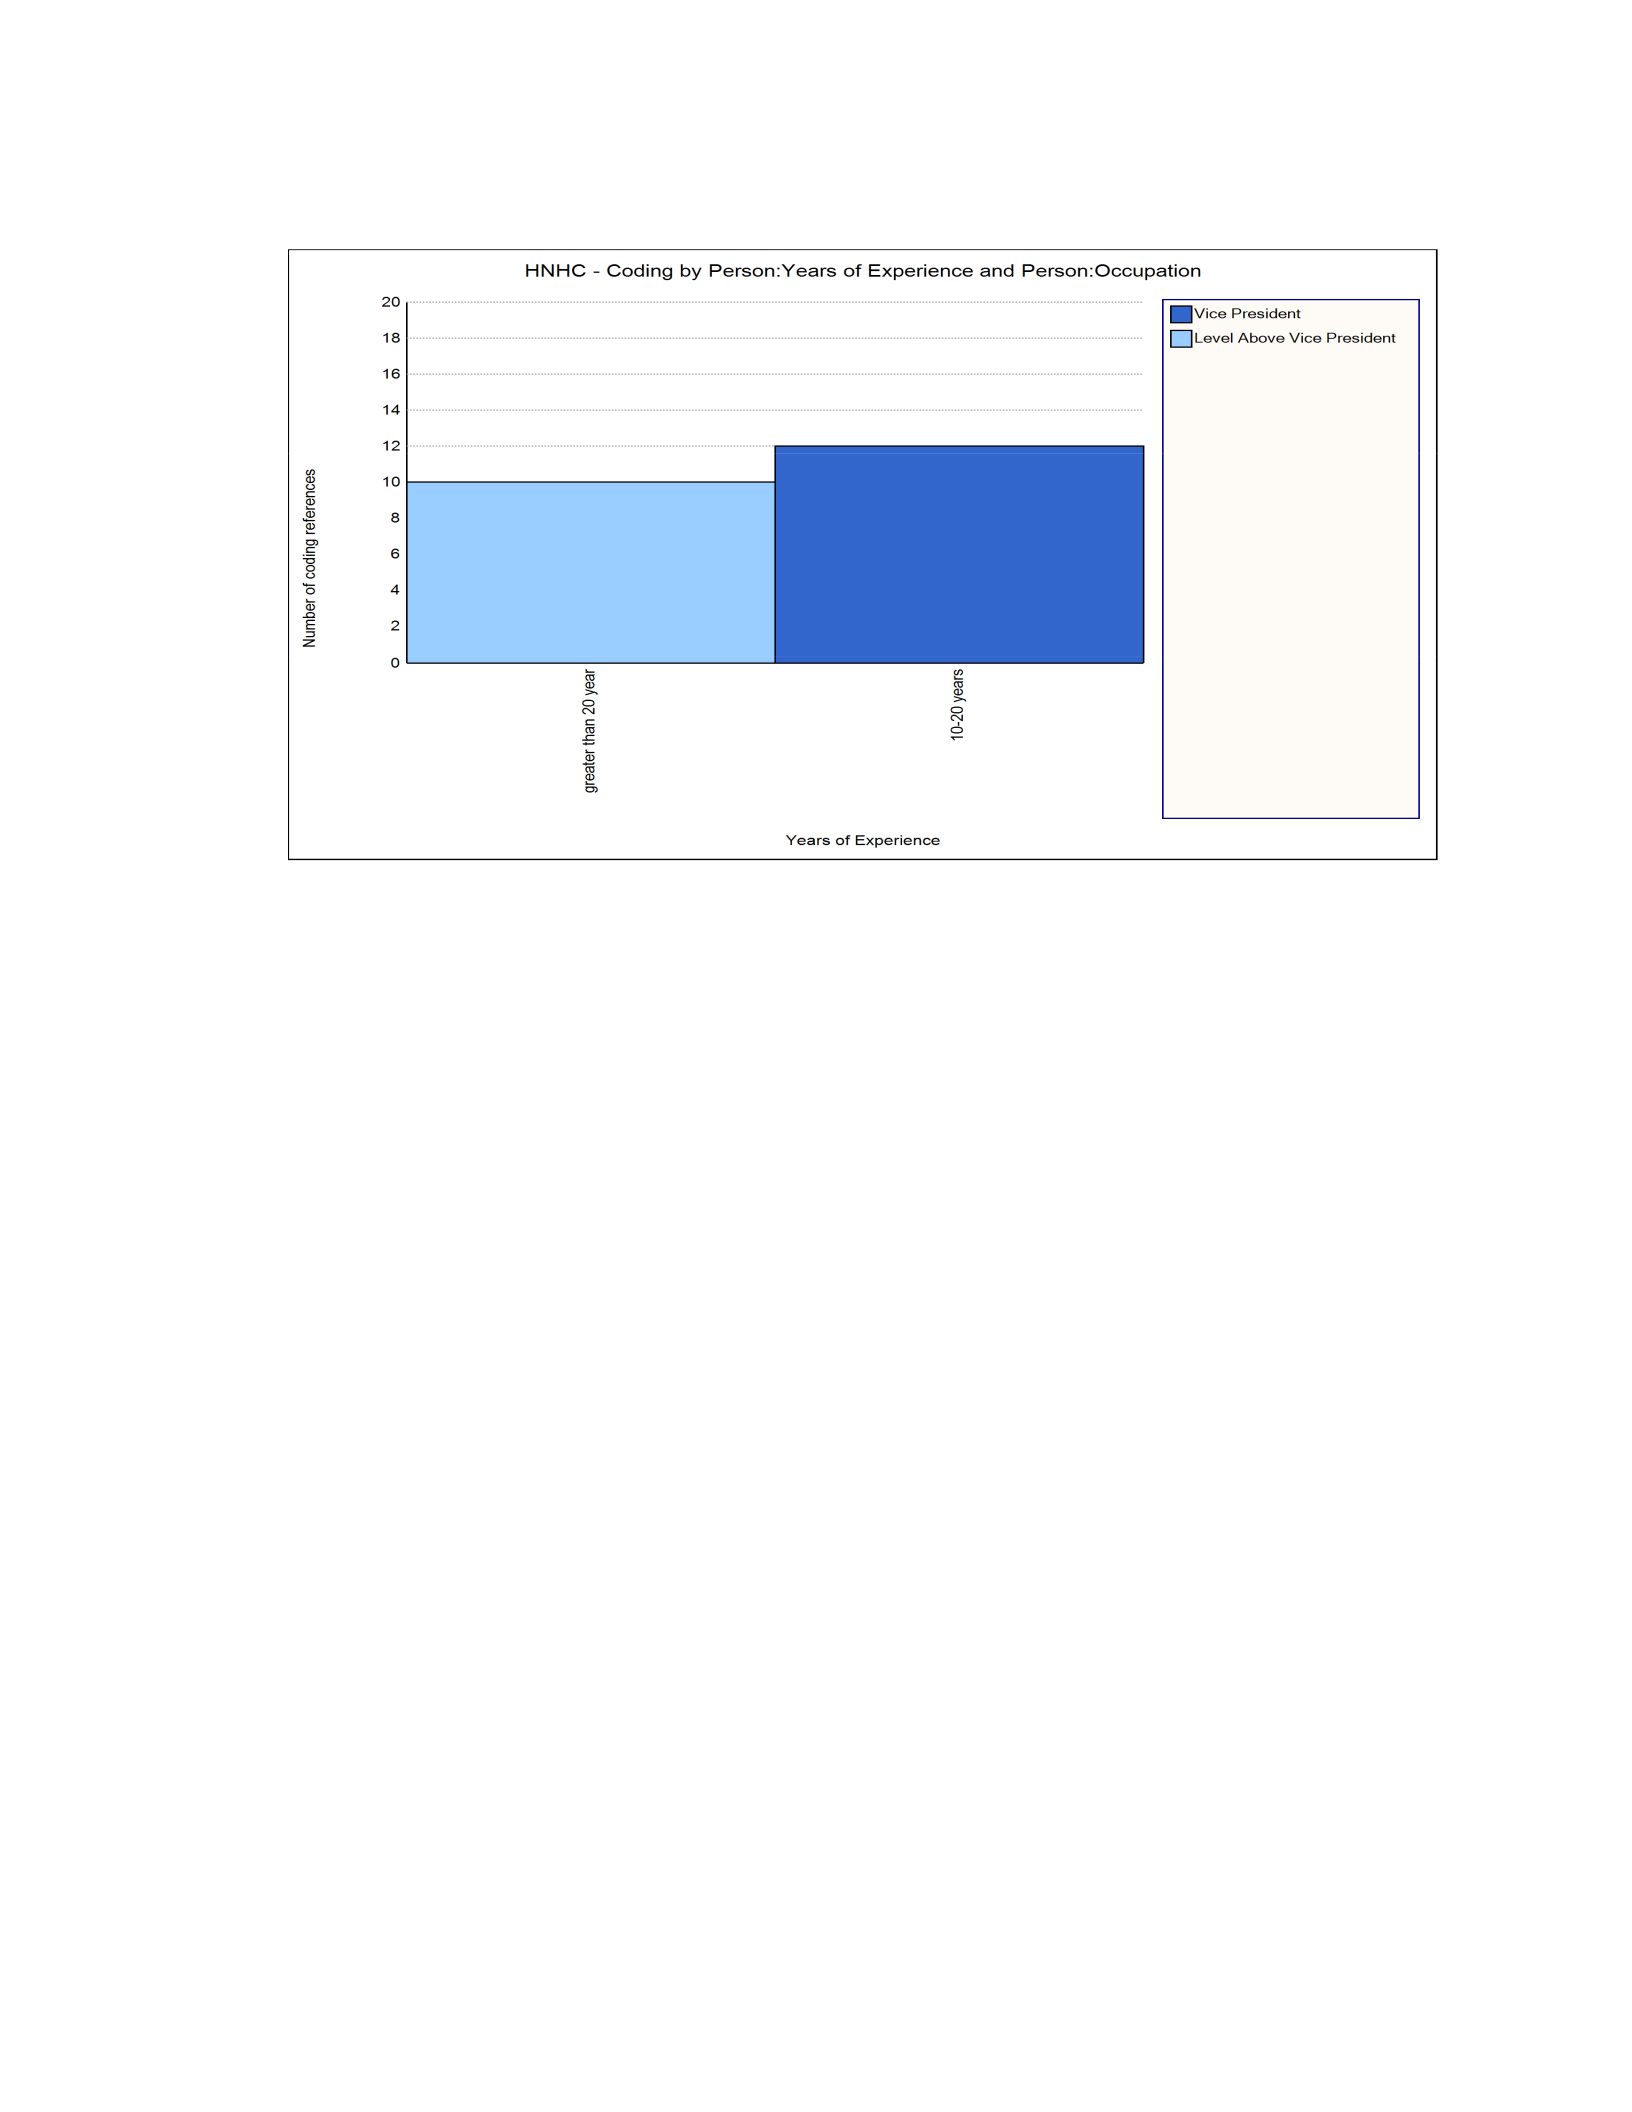
73
Figure 2. High-needs, high-cost frequency by participant.
The care delivery model for the HNHC population should include a
multidisciplinary approach to providing services (Hochman & Asch, 2016), confirming
the finding for 83% of the participants in the current study. Specifically, 5 (83%) of the
participants stated that health care leaders should specify that the HNHC population
requires interprofessional collaboration to impact cost. Jette (2016) indicated that the
characteristics of the HNHC population include three or more chronic conditions and
functional deficits. Moreover, Jiang et al. (2016) posited that the economically
disadvantaged populations have multiple factors beyond medical conditions that
influence health. Factors such as housing, access to food, transportation, and health
literacy affect readmission rates (Alvarez, Ginsberg, Grabowski, Post, & Rosenberg,
2016). Aligned with the TAM objectives, Taylor et al. (2016) noted that social
determinants of health are integral in influencing population health and improving quality

74
outcomes. Five (83%) of the participants in the current study identified a partnership with
primary care as a strategy for fostering support for care coordination programs aimed at
the HNHC population.
Theme 3: Partnership With Primary Care
Capital spending has an impact on the operating budget of health care
organizations, requiring health care leaders to make investments that reflect value and
improve population outcomes (Klein, Brown, & Detsky, 2016). Transforming the health
care delivery system to focus on cost and quality requires concentration on the role of
primary care providers (Miller et al., 2017). A strategy shared by 83% of the participants
in the current study included a partnership with primary care practices due to the ability
of primary care to lead cost containment strategies. Mostashari (2016) confirmed this
strategy by indicating that the decisions of the primary care physician impact 85% of the
cost of care; however, independent primary care providers may lack the financial
resources to invest in the technological advances, analytics, and human resources
required to provide value-based care. When reviewing the recent literature, I was able to
confirm that there is an opportunity to garner financial support for care coordination
programs through the partnership with primary care. Three (50%) of the participants in
the current study indicated that health care leaders should use innovative strategies to
integrate with primary care to meet the TAM objectives. Maciosek (2017) indicated that
primary care providers could align with value-based preventative measures to meet the
TAM objectives.

75
Theme 4: Patient-Centered Care
According to McWilliams and Schwartz (2017), care coordination programs have
a positive impact on patient experience. Farmanova et al. (2016) noted that care
coordination is a critical factor in providing patient-centered care. Likewise, Rowe et al.
(2016) posited that outcomes-based performance metrics centered on the patient and
family are necessary to define effective care management programs. When reviewing the
literature, I confirmed the findings that patient experience is a defining strategy when
garnering financial support for care coordination programs. Five (83%) participants in the
current study agreed that the perception of the patient population is a critical factor when
gaining support for care coordination programs. However, Farmanova et al. noted that
presenting patient experience data for a population is more difficult that collecting data at
a project level. According to one participant in the current study, patient-centered care
requires a comprehensive training process to develop care coordination practices among
team members.
Findings Related to the Triple Aim Model
The research findings were consistent with the TAM. The TAM objectives
include reducing per capita costs, achieving population health, and improving the patient
experience (Bodenheimer & Sinsky, 2014). According to Ryan, Brown, Glazier, and
Hutchison (2016), the predominant goal of the TAM is to accomplish the three objectives
simultaneously. The themes identified in the current study indicated successful
approaches used to populate the TAM framework. The findings reflect that the tenets of

76
the TAM are key in presenting strategies to garner support for care coordination
programs.
The TAM is essential in identifying strategies to reduce health care waste and
decrease costs (Coyne et al., 2016). Although medical care accounts for 10% to 20% of
the factors driving heath status, health care leaders attribute 88% of health care spending
to providing medical care (Zangerle, Harris, Rimmasch, & Randazzo, 2016). All
participants in the current study identified a reduction in health care cost as the most
successful strategy used to foster support for care coordination resources. Also, the
participants in this study identified medical care based measures to populate the TAM
objective of reducing health care cost. Therefore, based on the research findings,
successful strategies for garnering support for care coordination programs address the
component of health care that accounts for the largest percent of spending. On the other
hand, Zangerle et al. (2016) indicated that effective programs must address the upstream
social factors that have the greatest impact on health outcomes.
Defining the needs of the population is a core requirement for achieving the TAM
objectives (Farmanova et. al, 2016). According to Farmanova et al., health care leaders
define the population by a common need within a geographical region or by a distinct
population driven by business requirements. Whittington et al. (2015) noted that health
care leaders must choose populations whereby the three objectives of TAM apply. The
participants in the current study revealed the HNHC population as the population health
care leaders should address when appealing for financial support. Also, Kindig and Isham
(2014) posited that population health requires the collaboration of numerous

77
organizations to influence the social and physical determinants of health. Farmanova et
al. posited that organizational leaders must form cross-sector partnerships to implement
programs designed at meeting the TAM objectives. The research findings included the
partnership with primary care practice as a successful strategy to gain resource allocation
for care coordination program. The participants confirmed that health care leaders should
seek alliances with organizations to impact the TAM objectives.
According to Harder et al. (2016), measuring the TAM objective of patient
experience is a critical component in efforts to change the delivery of health care. Cook et
al. (2015) revealed that efforts to improve health outcomes must take account of patient
experience feedback to guide quality initiatives. Moreover, Ryan et al. (2016) indicated
that health care leaders could use patient surveys to establish a quantitative measure of
the patient experience TAM objective. The participants revealed an opportunity to use
patient experience surveys to provide feedback to senior executives regarding the
effectiveness of care coordination programs. The participants indicated that a strong
alignment with the patient-centered mission of the organization is
Applications to Professional Practice
The most prevalent finding relevant to the professional practice of business was
defining the ability of care coordination programs to reduce health care cost. The finding
is important to the practice of business because it provides a mechanism to garner
financial support for care coordination grounded in cost control strategies. In review of
recent literature, cost control was a critical factor in the development of care coordination
programs and aligns with the TAM. Miller et al. (2017) indicated that reducing cost and

78
improving the quality of care require health care leaders to invest in the transformation of
the health care delivery system.
Ellner and Phillips (2017) noted that health care leaders have the capacity to lead
the effort to transform the health care industry to provide high quality care at a
sustainable cost by focusing on the transformation of primary care practices. Similarly,
Cross, Cohen, Lemak, Adler-Mil-Stein (2017) indicated that policy leaders focused on
primary care to impact the cost and quality of health care. However, transitioning the
primary care model requires human resource investment and defined interprofessional
practices to reduce fragmentation and influence cost (Zink, Kralewski, & Dowd, 2017).
Mostashari (2016) added that primary care providers may lack the resources to invest in
value based care. Moreover, Whittington et al. (2015) posited that provider payments
lack incentives for providers to decrease the cost of health care. The findings are relevant
to the professional business practices, in that, the participants revealed that a strategic
alliance with primary care has the capacity influence investment in care coordination and
impact health care costs. Moreover, the research participants revealed an opportunity to
align with primary care practices and support incentives that encourage primary care
physicians to reduce costs associated with hospitalizations and emergency room
utilization.
Reinhard (2013) posited that managed care leaders with the capacity to coordinate
care for high-risk populations would increase profitability and market share. Therefore,
health care leaders could develop strategies to garner support for care coordination based
on methods to improve profitability. Cross et al. (2017) indicated that health care leaders

79
focus on improving health care cost by targeting the HNHC population that consume a
disproportionate share of health care services. Similarly, Jette (2016) indicated that the
HNHC population account for an approximate 50% of the total health care cost. In
relation to the applicability to the professional practice of business, the research
participants revealed that health care leaders should focus on the HNHC population when
presenting strategies for care coordination. In addition, the participants revealed that a
focus on the HNHC population provides a targeted approach to reveal a return on
investment for care coordination for a high cost group. Also, the research participants
indicated that the cost control data varies based on the maturity of the organization. Less
mature organizations might require health care consultants to conduct an environmental
scan to provide cost-effective strategies for care coordination. Health care leaders may
consider this finding critical to the professional practice of business because the maturity
of the managed care organization may influence the strategies required to garner financial
support. According to recent literature, the strategies health care leaders deploy are highly
dependent upon the organizational structures and processes (Aveling, Martin, Herbert, &
Armstrong, 2017).
According to Miller et al. (2017), the United States health care costs are
approximately $2.9 trillion and are not tantamount to an increase in quality. Health care
leaders use TAM to describe the health care agenda for systematic changes for cost
control (Bodenheimer & Sinsky, 2014). However, recent literature reflects that health
care leaders struggle with the practical application of the TAM objectives due to the
diverse comprehension of the relationship between quality and cost (Storkholm,

80
Mazzocato, Savage, & Savage, 2017). The findings are relevant to the professional
practice of business, in that, the participants in the current study provided health care
leaders a method to align the request for resource allocation with the TAM objective of
reducing cost.
Implications for Social Change
Health care leaders define population health as the clinical outcomes of a defined
group of individuals (Kindig & Isham, 2014). Population health is one of the three goals
of the TAM (Bodenheimer & Sinsky, 2014). In addition, a driver of population health is
transforming the medical culture from providing sick care to the provision of wellness
services to prevent illness (McGough, Kline, & Simpson, 2017). According to Shrank
(2017), the mission of primary care practices is to improve population health through the
provision of high-quality care. Health care leaders may consider the findings of this study
important to impact social change because garnering support for care coordination
programs grounded in the TAM objective of population health allows leaders to impact
the health of communities.
According to Zangerle et al. (2016), social determinants of health influence 80%
to 90% of the population’s health outcomes. Bridger, Smith, and Saunders (2017) posited
that the drivers of health status include social components that require a collective
approach to population health. Moreover, Taylor et al. (2016) indicated that
policymakers should take note of care coordination strategies that focus on social
determinants that impact overall population health and impact cost. Therefore, health care

81
leaders seeking to influence social change could use the results of this study to affect the
quality of care for the HNHC populations through care coordination programs.
MCOOA accounts for 25% of the enrollment for beneficiaries with federal and
state sponsored health care benefits (Reid et al., 2013). In addition, the dual-eligible
population is increasing at a rate that is double the beneficiaries of a single program
(Eggbeer et al., 2013). Moreover, the dual-eligible population is at greater risk for
fragmented care related to the need to coordinate between multiple programs with varied
benefits (Kennedy, 2013). Ortega (2016) posited that the dual-eligible have complex
social issues influencing access to health benefits. Powers et al. (2015) revealed that care
coordination programs could improve the quality of life and reduce health care
expenditures. The data from this study may affect social change by providing an avenue
through care coordination programs to reduce care fragmentation and address the social
determinants of health for a targeted high needs population.
Recommendations for Action
Rowe et al. (2016) indicated that evidence-based literature supports the need for
care coordination programs; however, health care leaders may lack the budget for
program implementation. The research findings provide strategies to garner support for
programs grounded in the TAM objectives. Based on the research findings, I recommend
the following actions:
• Leaders should define the measures used to populate the tenets of the TAM.

82
• Health care leaders should understand the mission of the organization and
focus on the patient driven elements when developing strategies for financial
support.
• Health care leaders should identify the hospital-based utilization measures that
support the mission of the organization.
• Leaders should focus on the high-need, high-cost population and consider the
dual-eligible as a priority population.
• Health care leaders should identify stakeholders within primary care to create
an interprofessional practice environment to support medical and social
determinants of health.
• Health care leaders should gauge the maturity of the organization and shape
discussions to ensure a comprehensive understanding of managed care and
care coordination.
The findings are broadly applicable to health care organizations that are
accountable for care coordination programs. I will seek to disseminate findings through
academic journals and professional conferences. Moreover, health care leaders could use
the results of the study to provide leadership development training for leaders responsible
for care coordination programs.
Recommendations for Further Research
There is a limit in literature defining a specific methodology to communicate the
financial benefits of care coordination program (Kripalani et al., 2014). The findings
from my study may contribute to limitations in research on business practices that health

83
care leaders can use to support financial allocations to care coordination programs.
Variability exists amongst program infrastructure and maturity of the organization.
Therefore, the recommendation for future research is to determine if there is a correlation
between the maturity of the managed care organization and the strategies used to garner
support. I utilized a single-case study design, which limits the research. I would
recommend that future research includes a multiple-case study design to increase the
sample size and improve generalizability. Also, I would recommend further research on
the care coordination program infrastructure and the impact on investment potential.
Reflections
I explored the strategies health care leaders use to garner financial support for
care coordination programs. I used reflexive journaling to document preconceptions and
personal bias. As an inside researcher, I was aware of my obligation to mitigate bias
through the preservation of reflexivity. I maintained the use of the interview protocol and
wad careful not to lead the participant during interview process. There were four
preconceived ideas discovered in the journaling process. Through the journaling process,
I revealed a preconceived idea that using external consultants reflected a lack of trust in
the experience of the internal leadership. After completing the study, my thoughts on the
value of external consultants changed to view the use of external consultants as a
reflection of the maturity of the organization and the commitment to identify best
practices beyond the walls of the organization. Second, I had a preconceived idea that the
strategies used in an integrated delivery system for the older adult with less than 2,000
members would differ from those used in a managed care environment with greater than

84
200,000 members. The health care leaders (50%) provided confirmation that the capacity
to provide care in an integrated model is significantly different. However, developing
programs with similar infrastructure and management strategies can prove beneficial and
applicable in settings focused on the HNHC population. Therefore, my thoughts
expanded to realizing the value of an analysis of best practices and the capacity to
replicate. The next preconceived idea was that primary care practice is a customer of the
managed care organization’s care coordination program. The study participants revealed
a partnership that required sharing goals, shared strategies, and shared knowledge to
achieve the TAM versus a customer-based relationship. The final preconceived idea was
that strategies for investment in care coordination programs required changing patient
behaviors; therefore, requiring a long-term commitment to realize savings. The study
participants revealed that strategies should focus on short-term savings realized through
risk pool savings and hospital utilization for the high cost population.
Summary and Study Conclusions
The purpose of this qualitative single-case study was to explore the strategies that
health care leaders use to improve corporate financial investment in care coordination
programs that include TAM objectives. The target population was health care leaders in
the role of vice president or higher who have implemented strategies to improve
corporate financial investment for care coordination programs. I conducted semi-
structured interviews and used open-ended questions to extract interview data. In
addition, I used archival documents (meeting minutes) for triangulation of the data to
address the research question. The five themes that emerged included (a) reflecting a

85
reduction in health care cost, (b) focusing on high-need, high-cost populations, (c)
partnering with primary care practices, and (d) providing patient satisfaction data. The
research participants revealed that defining the measures used to populate the key tenets
of the TAM objectives is of greater importance than citing the TAM. As a priority, health
care leaders seeking investment in care coordination must have a concise presentation
that reflects the cost considerations based on the level of risk assumed by the managed
care organization. Next, leaders should seek out alliances with primary care practices to
influence the population with the highest needs and highest cost. Finally, the research
reflected that there should be clear patient experience data to reflect the impact on the
population.

86
References
Alvarez, R., Ginsburg, J., Grabowski, J., Post, S., & Rosenberg, W. (2016). The social
work role in reducing 30-day readmissions: The effectiveness of the bridge model
of transitional care. Journal of Gerontological Social Work, 59(3), 222-227.
doi:10.1080/01634372.2016.1195781
Anderson, D., & Bjarnadóttir, M. (2016). When is an ounce of prevention worth a pound
of cure? Identifying high-risk candidates for case management. IIE Transactions
on Healthcare Systems Engineering, 6(1), 22-32.
doi:10.1080/19488300.2015.1126874
Aronson L., Bautista C. A., & Covinsky, K. (2015). Medicare and care coordination:
Expanding the clinician’s toolbox. Journal of the American Medical Association
313(8), 797-798. doi:10.1001/jama.2014.18174.
Auerbach, D. I., Liu, H., Hussey, P. S., Lau, C., & Mehrotra, A. (2013). Accountable care
organization formation is associated with integrated systems but not high medical
spending. Health Affairs, 32(10), 1781-8. doi:10.1377/hlthaff.2013.0372
Aveling, E. L., Martin, G., Herbert, G., & Armstrong, N. (2017). Optimising the
community-based approach to health care improvement: Comparative case studies
of the clinical community model in practice. Social Science & Medicine, 173, 96-
103. doi:10.1016/j.socscimed.2016.11.026
Baicker, K., Chernew, M., & Robbins, J. (2013). The spillover effects of Medicare
managed care: Medicare Advantage and hospital utilization. Journal of Health
Economics, 32(6), 1289-1300. doi:10.3386/w19070

87
Barratt, M., Choi, T. Y., & Li, M. (2011). Qualitative case studies in operations
management: Trends, research outcomes, and future research implications.
Journal of Operations Management, 29(4), 329-342.
doi:10.1016/j.jom.2010.06.002
Bekhet, A. K., & Zauszniewski, J. A. (2012). Methodological triangulation: An approach
to understanding data. Nurse Researcher, 20(2), 40-43.
doi:10.7748/nr2012.11.20.2.40.c9442
Berger, R. (2015). Now I see it, now I don’t: Researcher’s position and reflexivity in
qualitative research. Qualitative Research, 15(2), 219-234.
doi:10.1177/1468794112468475
Berkowitz, S. A., & Pahira, J. J. (2014). Accountable care organization readiness and
academic medical centers. Academic Medicine, 89(9), 1210-1215.
doi:10.1097/ACM.0000000000000365
Bernabeo, E., & Holmboe, E. S. (2013). Patients, providers, and systems need to acquire
a specific set of competencies to achieve truly patient-centered care. Health
Affairs, 32(2), 250-258. doi:10.1377/hlthaff.2012.1120
Bernauer, J. A., Lichtman, M., Jacobs, C., & Robinson, S. (2013). Blending the old and
the new: Qualitative data analysis as critical thinking and using NVivo with a
generic approach. Qualitative Report, 18(31), 1-10. Retrieved from
http://www.nova.edu/ssss/QR/index.html

88
Berwick, D. M., Feeley, D., & Loehrer, S. (2015). Change from the inside out: Health
care leaders taking the helm. Journal of the American Medical Association,
313(17), 1707-1708. doi:10.1001/jama.2015.2830
Black, J. D., Palombaro, K. M., & Dole, R. L. (2013). Student experiences in creating
and launching a student-led physical therapy pro bono clinic: A qualitative
investigation. Physical Therapy, 93(5), 637-48. doi:10.2522/ptj.20110430
Blumenthal, D., Chernof, B., Fulmer, T., Lumpkin, J., & Selberg, J. (2016). Caring for
high-need, high-cost patients. An urgent priority. New England Journal of
Medicine, 375(10), 909-911. doi:10.1056/NEJMp1608511
Blythe, S., Wikles, L., Jackson, D., & Halcomb, E. (2013). The challenges of being an
insider in storytelling research. Nurse Researcher, 21(1), 8-13.
doi:10.7748/nr2013.09.21.1.8.e333
Bodenheimer, T., & Sinsky, C. (2014). From triple to quadruple aim: Care of the patient
requires care of the provider. Annals of Family Medicine, 12(6), 573-576.
doi:10.1370/afm.1713
Bohren, M. A., Hunter, E. C., Munthe-Kaas, H. M., Souza, J. P., Vogel, J. P., &
Gülmezoglu, A. M. (2014). Facilitators and barriers to facility-based delivery in
low- and middle-income countries: A qualitative evidence synthesis.
Reproductive Health, 11, 71. doi:10.1186/1742-4755-11-71
Bridger, C. M., Smith, S. E., & Saunders, S. T. (2017). Saving lives and saving money:
The role of North Carolina health departments in Medicaid managed care. North
Carolina Medical Journal, 78(1), 55-57. doi:10.18043/ncm.78.1.55

89
Brown, J., Duggan, M., Kuziemko, I., & Woolston, W. (2014). How does risk selection
respond to risk adjustment? New evidence from the Medicare Advantage
Program. The American Economic Review, 104(10), 3335-3364.
doi:10.1257/aer.104.10.3335
Brown, R. S., Peikes, D., Peterson, G., Schore, J., & Razafindrakoto, C. M. (2012). Six
features of Medicare coordinated care demonstration programs that cut hospital
admissions of high-risk patients. Health Affairs, 31(6), 1156-1166.
doi:10.1377/hlthaff.2012.0393
Burda, M. H. F., van den Akker, M., van der Horst, F., Lemmens, P., & Knottnerus, J. A.
(2016). Collecting and validating experiential expertise is doable but poses
methodological challenges. Journal of Clinical Epidemiology, 72, 10-15.
doi:10.1016/j.jclinepi.2015.10.021
Caretta, M. A. (2015). Member checking: A feminist participatory analysis of the use of
preliminary results pamphlets in cross-cultural, cross-language research.
Qualitative Research, 16(3), 305-318. doi:10.1177/1468794115606495
Carroll, A. B. (2015). Corporate social responsibility. Organizational Dynamics, 44(2),
87-96. doi:10.1016/j.orgdyn.2015.02.002
Carter, N., Bryant-Lukosius, D., DiCenso, A., Blythe, J., & Neville, A. J. (2014). The use
of triangulation in qualitative research. Oncology Nursing Forum (41), 545-547.
doi:10.1188/14.ONF.545-547

90
Cason, J. (2015). Telehealth and occupational therapy: Integral to the triple aim of health
care reform. American Journal of Occupational Therapy, 69(2).
doi:10.5014/ajot.2015.692003
Chan, Z. C., Fung, Y. L., & Chien, W. T. (2013). Bracketing in phenomenology: Only
undertaken in the data collection and analysis process. The Qualitative Report,
18(30). Retrieved from http://www.nova.edu/ssss/QR/index.html
Chaysin, P., Daengdej, J., & Tangjitprom, N. (2016). Survey on available methods to
evaluate IT investment. Electronic Journal of Information Systems Evaluation,
19(1), 71-82. Retrieved from http://www.ejise.com
Cheng, B., Ioannou, I., & Serafeim, G. (2014). Corporate social responsibility and access
to finance. Strategic Management Journal, 35(1), 1-23. doi:10.1002/smj.2131
Chernev, A., & Blair, S. (2015). Doing well by doing good: The benevolent halo of
corporate social responsibility. Journal of Consumer Research, 41(6), 1412-1425.
doi:10.1086/680089
Cleave, J.H., Trotta, R., Lysaght, S., Steis, M., Lorenz, R., & Naylor, M. (2013).
Comorbidities in the context of care transitions. Advances in Nursing Science,
36(2), E1-D13. doi:10.1097/ANS.0b013e318290207d
Cohen, D., Huynh, T., Sebold, A., Harvey, J., Neudorf, C., & Brown, A. (2014). The
population health approach: A qualitative study of conceptual and operational
definitions for leaders in Canadian health care. Open Medicine, 2.
doi:10.1177/2050312114522618

91
Colla, C. H., Goodney, P. P., Lewis, V. A., Nallamothu, B. K., Gottlieb, D. J., & Meara,
E. (2014). Implementation of a pilot accountable care organization payment
model and the use of discretionary and nondiscretionary cardiovascular care.
Circulation, 130(22), 1954-1961. doi:10.1161/circulationaha.114.011470
Collins, C. S., & Cooper, J. E. (2014). Emotional intelligence and the qualitative
researcher. International Journal of Qualitative methods, 13, 88-103. Retrieved
from http://ejournals.library.ualberta.ca/index.php/IJQM
Cook, N., Hollar, L., Isaac, E., Paul, L., Amofah, A., & Shi, L. (2015). Patient experience
in health center medical homes. Journal of Community Health, 40(6), 1155-1164.
doi:10.1007/s10900-015-0042-0
Coughlin, T. A., Waidmann, T. A., & Phadera, L. (2012). Among dual eligibles,
identifying the highest-cost individuals could help in crafting more targeted and
effective responses. Health Affairs, 31(5), 1083-91.
doi:10.1377/hlthaff.2011.0729
Coyne, J. S., Hilsenrath, P. E., Arbuckle, B. S., Kureshy, F., Vaughan, D., Grayson, D., &
Saygin, T. (2014). Triple aim program: Assessing its effectiveness as a hospital
management tool. Hospital Topics, 92(4), 88-95.
doi:10.1080/00185868.2014.968488.
Craver, G., Cuellar, A., & Gimm, G. (2016). Evaluating commonwealth coordinated care:
The experiences of individuals dually eligible for Medicare and Medicaid. Age in
Action, 31(3), 1. Retrieved from scholarscompass.vcu.edu

92
Cross, D. A., Cohen, G. R., Lemak, C. H., & Adler-Milstein, J. (2017). Outcomes for
high-needs patients: Practices with a higher proportion of these patients have an
edge. Health Affairs, 36(3), 476-484. doi:10.1377/hlthaff.2016.1309
Cutler, A., Rich, A., & Yee, S. (2013). Advocate’s guide to California’s coordinated care
initiative. Retrieved from www.sandiegocounty.gov
Daveson, B. A., Harding, R., Shipman, C., Mason, B. L., Epiphaniou, E., Higginson, I. J.,
. . . Murray, S. (2014). The real-world problem of care coordination: A
longitudinal qualitative study with patients living with advanced progressive
illness and their unpaid caregivers. PLOS One, 9(5).
doi:10.1371/journal.pone.0095523
de Waal, H., Beaumont, J., & Mitchell, C. (2013). Developing a business case,
negotiating, securing funding. Designing and Delivering Dementia Services, 201-
214. doi:10.1002/9781118378663.ch15
Denzin, N. K., & Lincoln, Y. S. (2011). Sage Handbook of Qualitative Research.
Thousand Oaks, California: Sage Publications.
Desjardins, K. (2015). Comprehensive care coordination: The time is now. Clinical
Scholars Review, 8(1), 22. 22. doi:10.1891/1939-2095.8.1.2
Dharmarajan, K., Hsieh, A. F., Lin, Z., Bueno, H., Ross, J. S., Horwitz, L. I.,…Drye, E.
E. (2013). Diagnoses and timing of 30-day readmissions after hospitalization for
heart failure, acute myocardial infarction, or pneumonia. JAMA, 309(4), 355-363.
doi:10.1001/jama.2012.216476.

93
Doody, O., & Noonan, M. (2013). Preparing and conducting interviews to collect data.
Nurse Researcher, 20(5), 28-32. doi:10.7748/nr2013.05.20.5.28.e327
Doyle, D., Emmett, M., Crist, A., Robinson, C., & Grome, M. (2016). Improving the care
of dual eligible patients in rural federally qualified health centers: The impact of
care coordinators and clinical pharmacists. Journal of Primary care and
Community Health, 7(2), 118-121. doi:10.1177/2150131915617297
Duan, N., Bhaumik, D. K., Palinkas, L. A., & Hoagwood, K. (2015). Optimal design and
purposeful sampling: Complementary methodologies for implementation
research. Administration and Policy in Mental Health and Mental Health Services
Research, 42(5), 524-532. doi:10.1007/s10488-014-0596-7
Eapen, Z. J., Lauer, M. S., & Temple, R. J. (2014). The imperative of overcoming
barriers to the conduct of large, simple trials. JAMA, 311(14), 1397-1398.
doi:10.1001/jama.2014.1030
Eccles, R. G., Ioannou, I., & Serafeim, G. (2014). The impact of corporate sustainability
on organizational processes and performance. Management Science, 60(11),
2835-2857. doi:10.3386/w17950
Eggbeer, B., Bowers, K., & Morris, D. (2013). Dual-eligible reform: A step toward
population health management. Journal of the Healthcare Financial Management
Association, 67(4), 90. Retrieved from hfma.org
Ellner, A. L., & Phillips, R. S. (2017). The coming primary care revolution. Journal of
General Internal Medicine, 32(4), 380. doi:10.1007/s11606-016-3944-3

94
Elo, S., Kääriäinen, M., Kanste, O., Pölkki, T., Utriainen, K., & Kyngäs, H. (2014).
Qualitative content analysis. Sage Open, 4(1). doi:10.1177/2158244014522633
Enthoven, A. C. (2016). What is an integrated health care financing and delivery system
(IDS) and what must would-be IDS accomplish to become competitive with them.
Journal of Health Economics and Outcomes Research, 2(115), 2. Retrieved from
www.jheor.org/index.php/about-us/about-jheor
Farmanova, E., Kirvan, C., Verma, J., Mukerji, G., Akunov, N., Phillips, K., & Samis, S.
(2016). Triple aim in Canada: Developing capacity to lead to better health, care
and cost. International Journal for Quality in Health Care, 28(6): 830-837.
doi:10.1093/intqhc/mzw118
Feltner, C., Jones, C. D., Cené, C. W., Zheng, Z., Sueta, C. A., Coker-Schwimmer, E.
L.,…Jonas, D. E. (2014). Transitional care interventions to prevent readmissions
for persons with heart failure: A systematic review and meta-analysis. Annals of
Internal Medicine, 160(11), 774-784. doi:10.7326/M14-0083
Findley, S., Matos, S., Hicks, A., Chang, J., & Reich, D. (2014). Community health
worker integration into the health care team accomplishes the triple aim in a
patient-centered medical home: A Bronx tale. The Journal of Ambulatory Care
Management, 37(1), 82-91. doi:10.1097/jac.0000000000000011
Fischer, C., Lingsma, H. F., Marang-van de Mheen, P. J., Kringos, D. S., Klazinga, N. S.,
& Steyerberg, E. W. (2014). Is the readmission rate a valid quality indicator: A
review of the evidence. Plos ONE, 9(11), 1-9. doi:10.1371/journal.pone.0112282

95
Frank, R. G. (2013). Using shared savings to foster coordinated care for dual eligibles.
The New England Journal of Medicine, 368(5), 404-5.
doi:10.1056/nejmp1214155
Frank, L., Basch, E., & Selby, J. V. (2014). The PCORI perspective on patient-centered
outcomes research. JAMA, 312(15), 1513-1514.
doi:10.1001/jama.2014.11100
Franklin, G. M., & Busis, N. A. (2016). The AAN and the triple aim. Neurology, 86(2),
114-115. doi:10.1212/wnl.0000000000002120
Fuse-Brown, E. C. (2015). The blind Spot in the Patient Protection and Affordable Care
Act’s cost-control policies. Annals of Internal Medicine, 163(11), 871-872.
doi:10.7326/M15-1386
Gage, B., & Albaroudi, A. (2015). The triple aim and the movement toward quality
measurement of family caregiving. Generations, 39(4), 28-33. Retrieved from
www.asaging.org
George, V. M., & Shocksnider, J. (2014). Leaders, are you ready for change: The clinical
nurse as care coordinator in the new health care system. Nursing Administration
Quarterly, 38(1), 78-85. doi:10.1097/NAQ.0000000000000011
Gimm, G., Blodgett, E., & Zanwar, P. (2016). Examining access to care for younger vs.
older dual-eligible adults living in the community. Disability and Health Journal,
9(3), 431-438. doi:10.1016/j.dhjo.2015.12.004
Gohil, S. K., Datta, R., Cao, C., Phelan, M. J., Nguyen, V., Rowther, A. A., & Huang, S.
S. (2015). Impact of hospital population case-mix, including poverty, on hospital

96
all-cause and infection-related 30-day readmission rates. Clinical Infectious
Diseases, 61(8), 1235-1243. doi:10.1093/cid/civ539
Golden, A. (2015). What is an accountable care organization. The Journal for Nurse
Practitioners, 11(8), 843-844. doi:10.1016/j.nurpra2015.06.007
Greene, M. J. (2014). On the inside looking in: Methodological insights and challenges in
conducting qualitative insider research. Qualitative Report, 19(29), 1-13.
Retrieved from http://www.nova.edu/ssss/QR/index.html
Gu, Q., Koenig, L., Faerberg, J., Steinberg, C., Vaz, C., & Wheatley, M. P. (2014). The
Medicare hospital readmissions reduction program: Potential unintended
consequences for hospitals serving vulnerable populations. Health Services
Research, 49(3), 818-837. doi:10.1111/1475-6773.12150
Gulati, R. (2013). Readmissions: A quality metric with financial penalties. Journal of
Community Hospital Internal Medicine Perspectives, 3(1), 20219.
doi:10.3402/jchimp.v3i1.20219.
Hacker, K., & Walker, D. K. (2013). Achieving population health in accountable care
organizations. American Journal of Public Health, 103(7), 1163-1167.
doi:10.2105/AJPH.2013.301254
Hahn, K. A., Gonzalez, M. M., Etz, R. S., & Crabtree, B. F. (2014). National committee
for quality assurance (NCQA) patient-centered medical home (PCMH)
recognition is suboptimal even among innovative primary care practices. The
Journal of the American Board of Family Medicine, 27(3), 312-313.
doi:10.3122/jabfm.2014.03.130267

97
Hahn, T., Figge, F., Aragon-Correa, J.A., & Sharma, S. (2015). Advancing research on
corporate sustainability: Off to pastures new or back to the roots. Business &
Society,
56(2), 155-185. doi:10.1177/0007650315576152
Hahn, T., Pinkse, J., Preuss, L., & Figge, F. (2015). Tensions in corporate sustainability:
Towards an integrative framework. Journal of Business Ethics, 127(2), 297-316.
doi:10.1007/s10551-014-2047-5
Halaweh, M. (2012). Integration of grounded theory and case study: An exemplary
application from e-commerce security perception research. Journal of Information
Technology Theory and Application, 13(1), 31-50. doi:10.4301/s1807-
17752012000100002
Hall, M. A. (2014). Evaluation of the Affordable Care Act: The eye of the beholder.
Houston Law Review, 51(4), 1029-1056. Retrieved from
http://www.houstonlawreview.org
Hamel, M. B., Blumenthal, D., Abrams, M., & Nuzum, R. (2015). The Affordable Care
Act at 5 years. The New England Journal of Medicine, 372(25), 2451-2458.
doi:10.1056/nejmc1510015
Hanson, J. L., Balmer, D. F., & Giardino, A. P. (2011). Qualitative research methods for
medical educators. Academic Pediatrics, 11(5), 375-386.
doi:10.1016/j.acap.2011.05.001.
Hao, W., Johnson, C., Robinson, R. D., Nejtek, V. A., Schrader, C. D., Leuck,
J.,…Zenarosa, N. R. (2016). Roles of disease severity and post-discharge

98
outpatient visits as predictors of hospital readmissions. BMC Health Services
Research, 16(1). doi:10.1186/s12913-016-1814-7
Harder, V. S., Krulewitz, J., Jones, C., Wasserman, R. C., & Shaw, J. S. (2016). Effects
of patient-centered medical home transformation on child patient experience. The
Journal of the American Board of Family Medicine, 29(1), 60-68.
doi:10.3122/jabfm.2016.01.150066
Harper, M., & Cole, P. (2012). Member checking: Can benefits be gained similar to
group therapy. Qualitative Report, 17(2), 510-517. Retrieved from
http://www.nova.edu/ssss/QR/QR17-2/harper.pdf
Harrington, S. E. (2013). Medical loss ratio regulation under the Affordable Care Act.
Inquiry, 50(1), 9-26. doi:10.2139/ssrn.2180965
Harvard Business Press. (2011). Developing a business case: Expert solutions to
everyday challenges. Boston, Massachusetts: Harvard Business School
Publishing.
Hays, D. G., & Wood, C. (2011). Infusing qualitative traditions in counseling research
designs. Journal of Counseling and Development, 89(3), 288-295.
doi:10.1002/j.1556-6678.2011.tb00091.x
Hellander, I., Himmelstein, D. U., & Woolhandler, S. (2013). Medicare overpayments to
private plans 1985–2012: Shifting seniors to private plans has already cost
Medicare $282.6 billion. International Journal of Health Services, 43(2), 305-
319. doi:10.2190/HS.43.2.g

99
Hendrikx, R. J., Drewes, H. W., Spreeuwenberg, M., Ruwaard, D., Struijs, J. N., & Baan,
C. A. (2016). Which triple aim related measures are being used to evaluate
population management initiatives: An international comparative analysis. Health
Policy,
120(5), 471–485. doi:10.1016/j.healthpol.2016.03.008
Hirsch, J. A., Barr, R. M., McGinty, G., Nicola, G. N., Schaefer, P. W., Silva, E., &
Manchikanti, L. (2014). Affordable care 2014: A tale of two boards. Journal of
Neurointerventional Surgery, 6(9), 718-720. doi:10.1136/neurintsurg-2014-
011322
Hibbard, J. H., & Greene, J. (2013). What the evidence shows about patient activation:
Better health outcomes and care experiences, fewer data on costs. Health Affairs,
32(2), 207-14. doi:10.1377/hlthaff.2012.1061
Hitch, B., Parlier, A. B., Reed, L., Galvin, S. L., Fagan, E. B., & Wilson, C. G. (2016).
Evaluation of a team-based, transition-of-care management service on 30-day
readmission rates. North Carolina Medical Journal, 77(2), 87-92.
doi:10.18043/ncm.77.2.87
Hochman, M., & Asch, S. M. (2017). Disruptive models in primary care: Caring for high-
needs, high-cost populations. Journal of General Internal Medicine, 32(4), 392-
397. doi:10.1007/s11606-016-3945-2
Hodin, R. M. (2013). The secret sauce is consumer stakeholder engagement.
Generations, 37(2), 88-94. Retrieved from www.asaging.org

100
Hofler, R. A., & Ortiz, J. (2016). Costs of accountable care organization participation for
primary care providers: Early stage results. BMC Health Services Research,
16(1), 315. doi:10.1186/s12913-016-1556
Holloway, I. & Wheeler, S. (2013). Qualitative research in nursing and health care.
Oxford, United Kingdom: John Wiley & Sons.
Hong, C. S., Siegel, A. L., & Ferris, T. G. (2014). Caring for high-need, high-cost
patients: What makes for a successful care management program. Issue Brief:
Common Wealth Fund, 19, 1-19. Retrieved from commonwealthfund.org
Houghton, C., Casey, D., Shaw, D., & Murphy, K. (2013). Rigour in qualitative case-
study research. Nurse Researcher, 20(4), 12-17.
doi:10.7748/nr2013.03.20.4.12.e326
Howard, J., Etz, R. S., Crocker, J. B., Skinner, D., Kelleher, K. J., Hahn, K.
A.,…Crabtree, B. F. (2016). Maximizing the patient-centered medical home
(PCMH) by choosing words wisely. The Journal of the American Board of
Family Medicine, 29(2), 248-253. doi:10.3122/jabfm.2016.02.150199
Hussein, A. (2015). The use of triangulation in social sciences research: Can qualitative
and quantitative methods be combined. Journal of Comparative Social Work,
4(1). Retrieved from http://jcsw.no
Husted, B. W., Montiel, I., & Christmann, P. (2016). Effects of local legitimacy on
certification decisions to global and national CSR standards by multinational
subsidiaries and domestic firms. Journal of International Business Studies, 47(3),
382-397. doi:10.1057/jibs.2016.3

101
Jackson, G. L., Powers, B. J., Chatterjee, R., Bettger, J. P., Kemper, A. R., Hasselblad,
V.,…Gray, R. (2013). The patient-centered medical home: A systematic review.
Annals of Internal Medicine, 158(3), 169-178. Retrieved from
http://www.annals.org
Jacob, S. A., & Furgerson, S. P. (2012). Writing interview protocols and conducting
interviews: Tips for students new to the field of qualitative research. The
Qualitative Report, 17(42), 1-10. Retrieved from
http://www.nova.edu/ssss/QR/index.html
Jain, S. H., & Shrank, W. H. (2014). The CMS innovation center: Delivering on the
promise of payment and delivery reform. Journal of General Internal Medicine,
29(9), 1221-1223. doi:10.1007/s11606-014-2844-7
Jette, A. M. (2016). Meeting the challenge of the high-need, high-cost population.
Physical Therapy, 96(11), 1682. doi:10.2522/ptj.2016.96.11.1682
Jiang, H. J., Boutwell, A. E., Maxwell, J., Bourgoin, A., Regenstein, M., & Andres, E.
(2016). Understanding patient, provider, and system factors related to Medicaid
readmissions. The Joint Commission Journal on Quality and Patient Safety,
42(3), 115-121. Retrieved from http://www.jcrinc.com
Johnson, B. H., Smoyer-Tomic, K. E., Siu, K., Walker, D. R., Sander, S., Huse,
D.,…Amin, A. (2013). Readmission among hospitalized patients with
nonvalvular atrial fibrillation. American Journal of Health-System Pharmacy,
70(5), 414-422. doi:10.2146/ajhp120461.

102
Joynt, K. E., Gawande, A., Orav, E.J, & Jha, A. K. (2013). Contribution of preventable
acute care spending to total spending for high-cost Medicare patients. JAMA,
309(24), 2572-2578. doi:10.1001/jama.2013.7103
Jung, H.-Y., Trivedi, A. N., Grabowski, D. C., & Mor, V. (2015). Integrated Medicare
and Medicaid managed care and rehospitalization of dual eligibles. The American
Journal of Managed Care, 21(10), 711–717. Retrieved from
http://www.ajmc.com/journals/issue/2016/2016-vol22-n1
Justice, D., & Holladay, S. (2013). A process with promise: How the new integration
demonstrations may align care for dual eligibles. Generations, 37(2), 13-20.
Retrieved from www.asaging.org
Kahlon, S., Pederson, J., Majumdar, S. R., Belga, S., Lau, D., Fradette, M.,…McAlister,
F. A. (2015). Association between frailty and 30-day outcomes after discharge
from hospital. Canadian Medical Association Journal, 187(11), 799-804.
doi:10.1503 /cmaj.150100
Kash, B. A., Spaulding, A., Johnson, C. E., & Gamm, L. (2014). Success factors for
strategic change initiatives: a qualitative study of health care administrators’
perspectives. Journal of Healthcare Management, 59(1), 65-81. Retrieved from
http://www.ache.org/PUBS/jhmsub.cfm
Kates, S. L., Shields, E., Behrend, C., & Noyes, K. K. (2015). Financial implications of
hospital readmission after hip fracture. Geriatric Orthopaedic Surgery and
Rehabilitation, 3(6), 140-146. doi:10.1177/2151458515578265

103
Katon, W. J., & Unützer, J. (2013). Health reform and the Affordable Care Act: the
importance of mental health treatment to achieving the triple aim. Journal of
Psychosomatic research, 74(6). doi:10.1016/j.jpsychores.2013.04.005
Kelleher, K. J., Cooper, J., Deans, K., Carr, P., Brilli, R. J., Allen, S., & Gardner, W.
(2015). Cost saving and quality of care in a pediatric accountable care
organization. Pediatrics, 135(3), e582-e589. doi:10.1542/peds.2014-2725d
Kelly, S. E. (2010). Qualitative interviewing techniques and styles. Qualitative Methods
in Health Research, 307-326. doi:10.4135/9781446268247.n17
Kennedy, M. (2013). Community-based health plans take the complex path to integrated
care. Generations, 37(2), 30-32. Retrieved from www.asaging.org
Kindig, D. A., & Isham, G. (2014). Population health improvement: A community health
business model that engages partners in all sectors. Frontiers of Health Services
Management, 30(4), 3-20.
King, B. J., Gilmore‐Bykovskyi, A. L., Roiland, R. A., Polnaszek, B. E., Bowers, B. J., &
Kind, A. J. (2013). The consequences of poor communication during transitions
from hospital to skilled nursing facility: A qualitative study. Journal of the
American Geriatrics Society, 61(7), 1095-1102. doi:10.1111/jgs.12328
Klein, D. J., Brown, A. D., & Detsky, A. S. (2016). Investing wisely in health care
capital. JAMA, 316(15), 1543-1544. doi:10.1001/jama.2016.10605
Kolb, S. M. (2012). Grounded theory and the constant comparative method: Valid
research strategies for educators. Journal of Emerging Trends in Educational

104
Research and Policy Studies, 3(1), 83. Retrieved from
http://jeteraps.scholarlinkresearch.com
Korschun, D., Bhattacharya, C. B., & Swain, S. D. (2016). CSR and the frontline context:
How social programs improve customer service. Marketing Intelligence Review,
8(1), 24-29. doi:10.1515/gfkmir-2016-0004
Kripalani, S., Theobald, C. N., Anctil, B., & Vasilevskis, E. E. (2014). Reducing hospital
readmission rates: Current strategies and future directions. Annual Review of
Medicine, 65(1), 471-485. doi:10.1146/annurev-med-022613-090415
Kull, A. J., Mena, J. A., & Korschun, D. (2016). A resource-based view of stakeholder
marketing. Journal of Business Research, 69(12), 5553-5560.
doi:10.1016/j.jbusres.2016.03.063
Landon, B. E., Zaslavsky, A. M., Saunders, R., Pawlson, L. G., Newhouse, J. P., &
Ayanian, J. Z. (2015). A comparison of relative resource use and quality in
Medicare Advantage health plans versus traditional Medicare. American Journal
of Managed Care, 21(8), 559-566. Retrieved from www.ajmc.com
Larson, I. A., Hoffman, A., & Artman, M. (2017). Maximizing health outcomes in a
medical home for children with medical complexity: The beacon program. The
Journal of Pediatrics, 183, 4-5. doi:10.1016/j.jpeds.2017.01.024
Lindeblad, M. (2013). Washington state implements two duals demonstration models.
Generations, 37(2), 21-23. Retrieved from www.asaging.org
Linnenluecke, M. K., Verreynne, M. L., de Villiers Scheepers, M. J., & Venter, C.
(2017). A review of collaborative planning approaches for transformative change

105
towards a sustainable future. Journal of Cleaner Production, 142, 3212-3224.
doi:10.1016/j.jclepro.2016.10.148
Lohle, M. F., & Terrell, S. R. (2014). Real projects, virtual worlds: Coworkers, their
avatars, and the trust conundrum. The Qualitative Report, 19(8), 1-35. Retrieved
from http://www.nova.edu/ssss/QR/
Lozano, R. (2015). A holistic perspective on corporate sustainability drivers. Corporate
Social Responsibility and Environmental Management, 22(1), 32-44.
doi:10.1002/csr.1325
Lucatorto, M. A., Watts, S. A., Kresevic, D., Burant, C. J., & Carney, K. J. L. (2016).
Impacting the trajectory of chronic kidney disease with ARPN-led renal teams.
Nursing Administration Quarterly, 40(1), 76-86.
doi:10.1097/naq.0000000000000148
Maciosek, M. V., LaFrance, A. B., Dehmer, S. P., McGree, D. A., Flottemesch, T. J., Xu,
Z., & Solberg, L. I. (2017). Updated priorities among effective clinical preventive
services. The Annals of Family Medicine, 15(1), 14-22. doi:10.1370/afm.2017
Maes, K., van Grembergen, W., & de Haes, S. (2013). Identifying multiple dimensions of
a business case: A systematic literature review. Electronic Journal of Information
Systems Evaluation, 16(4), 302-314. Retrieved from http://www.ejise.com
Mansell, S. (2013). Shareholder theory and Kant’s duty of beneficence. Journal of
Business Ethics, 117(3), 583-599. doi:10.1007/s10551-012-1542-9

106
Marek, K. D., Stetzer, F., Adams, S. J., Bub, L. D., Schlidt, A., & Colorafi, K. J. (2014).
Cost analysis of a home‐based nurse care coordination programs. Journal of the
American Geriatrics Society, 62(12), 2369-2376. doi:10.1111/jgs.13162
Marshall, B., Cardon, P., Poddar, A., & Fontenot, R. (2013). Does sample size matter in
qualitative research: A review of qualitative interviews in IS research. Journal of
Computer Information Systems, 54(1), 11-22.
doi:10.1080/08874417.2013.11645667
McDermid, F., Peters, K., Jackson, D., & Daly, J. (2014). Conducting qualitative research
in the context of pre-existing peer and collegial relationships. Nurse Researcher,
21(5), 28-33. doi:10.7748/nr.21.5.28.e1232
McGinley, E. L., & Gabbay, R. A. (2016). The impact of new payment models on quality
of diabetes care and outcomes. Current Diabetes Reports, 16(6), 1-4.
doi:10.1007/s11892-016-0743-5
McGough, P., Kline, & Simpson, L. (2017). Team care approach to population health and
care management. International Journal of Health Governance, 22(2), 93-103.
doi:10.1108/IJHG-11-2016-0048
McWilliams, J. M., & Schwartz, A. L. (2017). Focusing on high-cost patients: The key to
addressing high costs. The New England Journal of Medicine, 376(9), 807-809.
doi:10.1056/NEJMp1612779
Merriam, S. B. (2014). Qualitative research: A guide to design and implementation. San
Francisco, CA: John Wiley & Sons.

107
Mertens, D. M. (Ed.). (2014). Research and evaluation in education and psychology:
Integrating diversity with quantitative, qualitative, and mixed methods. Thousand
Oaks, CA: Sage Publications.
Mery, G., Majumder, S., Brown, A., & Dobrow, M. J. (2017). What do we mean when
we talk about the triple aim: A systematic review of evolving definitions and
adaptations of the framework at the health system level. Health Policy, 121, 629-
636. doi:10.1016/j.healthpol.2017.03.014
Miller, B. F., Ross, K. M., Davis, M. M., Melek, S. P., Kathol, R., & Gordon, P. (2017).
Payment reform in the patient-centered medical home: Enabling and sustaining
integrated behavioral health care. American Psychologist, 72(1), 55.
doi:10.1037/a0040448
Milne, M. J., & Gray, R. (2013). Whither ecology.The triple bottom line, the global
reporting initiative, and corporate sustainability reporting. Journal of Business
Ethics, 118(1), 13-29. doi:10.1007/s10551-012-1543-8
Miranda, M. L., Ferranti, J., Strauss, B., Neelon, B., & Califf, R. M. (2013). Geographic
health information systems: A platform to support the triple aim. Health Affairs,
32(9), 1608-1615. doi:10.1377/hlthaff.2012.1199
Mittler, J. N., O’Hora, J. L., Harvey, J. B., Press, M. J., Volpp, K. G., & Scanlon, D. P.
(2013). Turning readmission reduction policies into results: Some lessons from a
multistate initiative to reduce readmissions. Population health management,
16(4), 255-260. doi:10.1089/pop.2012.0087

108
Montiel, I., & Delgado-Ceballos, J. (2014). Defining and measuring corporate
sustainability. Are we there yet. Organization & Environment, 27(2), 113-139.
doi:10.5465/ambpp.2013.14570
Moreo, K., Moreo, N., Urbano, F. L., Weeks, M., & Greene, L. (2014). Are we prepared
for Affordable Care Act provisions of care coordination: Case managers’ self-
assessments and views on physicians’ roles. Professional Case Management,
19(1), 18-26. doi:10.1097/ncm.0000000000000013
Morley, M. A., Walsh, E. G., & Wilkin, J. C. (2013). Financing integrated care in the
financial alignment demonstration. Generations, 37(2), 24-29. Retrieved from
www.asaging.org
Morse, J. M., & Coulehan, J. (2015). Maintaining confidentiality in qualitative
publications. Qualitative Health Research, 25(2), 151-152.
doi:10.1177/1049732314563489
Morton, S., Shih, S. C., Winther, C. H., Tinoco, A., Kessler, R. S., & Scholle, S. H.
(2015). Health IT enabled care coordination: A national survey of patient-
centered medical home clinicians. The Annals of Family Medicine, 13(3), 250-
256. doi:10.1370/afm.1797
Mostashari, F. (2016). The paradox of size: How small, independent practices can thrive
in value-based care. The Annals of Family Medicine, 14(1), 5-7.
doi:10.1370/afm.1899
Moustakas, C. (1994). Phenomenological research methods. Thousand Oaks, CA: Sage
Publications.

109
Murphy, S. M., & Neven, D. (2014). Cost-effective: Emergency department care
coordination with a regional hospital information system. The Journal of
Emergency Medicine, 47(2), 223-231. doi:10.1016/j.jemermed.2013.11.073
Myers, M. D. (2013). Qualitative research in business and management. Thousand Oaks,
CA: Sage Publications.
Newhouse, J. P., & McGuire, T. G. (2014). How successful is Medicare Advantage.
Milbank Quarterly, 92(2), 351-394. doi:10.1111/1468-0009.12061
Nicol, E. D., Mohanna, K., & Cowpe, J. (2014). Perspectives on clinical leadership: A
qualitative study exploring the views of senior health care leaders in the UK.
Journal of the Royal Society of Medicine, 107(7), 277-286.
doi:10.1177/0141076814527274
O’Reilly, M., & Parker, N. (2013). Unsatisfactory saturation: A critical exploration of the
notion of saturated sample sizes in qualitative research. Qualitative Research,
13(2), 190-197. doi:10.1177/1468794112446106
Orentlicher, D. (2014). The future of the Affordable Care Act: Protecting economic
health more than physical health. Houston Law Review, 51(4). Retrieved from
http://www.houstonlawreview.org
Ortega, L. (2016). Patient empowerment for dual eligible: Teaching the most vulnerable
health plan members to manage their health. Professional Case Management,
21(1), 53-56. doi:10.1097/NCM.0000000000000132
Ory, M. G., Ahn, S., Jiang, L., Smith, M. L., Ritter, P. L., Whitelaw, N., & Lorig, K.
(2013). Successes of a national study of the chronic disease self-management

110
program: Meeting the triple aim of health care reform. Medical Care, 51(11),
992-998. doi:10.1097/mlr.0b013e3182a95dd1
Ouslander, J. G., & Maslow, K. (2012). Geriatrics and the triple aim: Defining
preventable hospitalizations in the long-term care population. Journal of the
American Geriatrics Society, 60(12), 2313-2318. doi:10.1111/jgs.12002
Palinkas, L. A., Horwitz, S. M., Green, C. A., Wisdom, J. P., Duan, N., & Hoagwood, K.
(2015). Purposeful sampling for qualitative data collection and analysis in mixed
method implementation research. Administration and Policy in Mental Health and
Mental Health Services Research, 42(5), 533–544. doi:10.1007/s10488-013-0528
Panzer, R. J., Gitomer, R. S., Greene, W. H., Webster, P. R., Landry, K. R., &
Riccobono, C. A. (2013). Increasing demands for quality measurement. JAMA,
310(18), 1971-1980. doi:10.1001/jama.2013.282047
Parina, R. P., Chang, D. C., Rose, J. A., & Talamini, M. A. (2015). Is a low readmission
rate indicative of a good hospital. Journal of the American College of Surgeons,
220(2), 169-176. doi:10.1016/j.jamcollsurg.2014.10.020
Peredaryenko, M. S., & Krauss, S. E. (2013). Calibrating the human instrument:
Understanding the interviewing experience of novice qualitative researchers. The
Qualitative Report, 18(43), 1. Retrieved from www.nsuworks.nova.edu/tqr/
Perry, A., & Stevens, A. B. (2013). How do we make the business case for transitions.
Generations, 36(4), 71-77. Retrieved from http://www.asaging.org

111
Pham, H. H., Cohen, M., & Conway, P. H. (2014). The pioneer accountable care
organization model: Improving quality and lowering costs. JAMA, 312(16), 1635-
1636. doi:10.1001/jama.2014.13109
Phillips, R. L., Bazemore, A. W., DeVoe, J. E., Weida, T. J., Krist, A. H., Dulin, M. F., &
Biagioli, F. E. (2015). A family medicine health technology strategy for achieving
the triple aim for US health care. Family medicine, 47(8), 628. Retrieved from
www.stfm.org
Picker, D., Heard, K., Bailey, T. C., Martin, N. R., LaRossa, G. N., & Kollef, M. H.
(2015). The number of discharge medications predicts thirty-day hospital
readmission: A cohort study. BMC Health Services Research, 15(1).
doi:10.1186/s12913-015-0950-9
Powers, B. W., Chaguturu, S. K., & Ferris, T. G. (2015). Optimizing high-risk care
management. JAMA, 313(8), 795-796. doi:10.1001/jama.2014.18171
Prina, L. (2016). Foundation grants to inform the Medicare debate. Health Affairs, 35(5),
932-933. doi:10.1377/hlthaff.2016.0383
Prindiville, K. (2013). The dual eligible demonstrations: Are current consumer
protections adequate. Generations, 37(2), 81-87. Retrieved from
http://www.asaging.org
Queen, P. (2015). Enlightened shareholder maximization: Is this strategy achievable.
Journal of Business Ethics, 127(3), 683-694. doi:10.1007/s10551-014-2070-6
Quinn, K. (2015). The 8 basic payment methods in health care. Annals of Internal
Medicine, 163(4), 300-306. doi:10.7326/M14-2784

112
Rabionet, S. E. (2011). How I learned to design and conduct semi-structured interviews:
An ongoing and continuous journey. Qualitative Report, 16(2), 563-566.
Retrieved from http://www.nova.edu/ssss/QR/index.html
Rahman, M., Keohane, L., Trivedi, A. N., & Mor, V. (2015). High-cost patients had
substantial rates of leaving Medicare Advantage and joining traditional Medicare.
Health Affairs, 34(10), 1675-1681. doi:10.1377/hlthaff.2015.0272
Rak, S., & Coffin, J. (2013). Affordable Care Act. The Journal of Medical Practice
Management, 28(5), 317. Retrieved from www.mpmnetwork.com
Rego, A., Cunha, M. P., & Polónia, D. (2015). Corporate sustainability: A view from the
top. Journal of Business Ethics, 143(1), 133-157. doi:10.1007/s10551-015-2760-8
Reid, R. O., Deb, P., Howell, B. L., & Shrank, W. H. (2013). Association between
Medicare Advantage plan star ratings and enrollment. JAMA, 309(3), 267-274.
doi:10.1001/jama.2012.173925
Reinhard, S. C. (2013). What do older adults want from integrated care. Generations,
37(2), 68-71. Retrieved from www.asaging.org
Ritchie, J., Lewis, J., Nicholls, C. M., & Ormston, R. (2013). Qualitative research
practice: A guide for social science students and researchers. Thousand Oaks,
CA: Sage Publications.
Rittenhouse, K., Harnish, C., Gross, B., Rogers, A., Miller, J. A., Chandler, R., & Rogers,
F. B. (2015). An analysis of geriatric recidivism in the era of accountable care
organizations. Journal of Trauma and Acute Care Surgery, 78(2), 409-414.
doi:10.1097/ta.0000000000000513

113
Rose, S., Zaslavsky, A. M., & McWilliams, J. M. (2016). Variation in accountable care
organization spending and sensitivity to risk adjustment: Implications for
benchmarking. Health Affairs, 35(3), 440-448. doi:10.1377/hlthaff.2015.1026
Rowe, J. W., Fulmer, T., & Fried, L. (2016). Preparing for better health and health care
for an aging population. JAMA, 316(16), 1643-1644.
doi:10.1001/jama.2016.12335
Rowley, J. (2012). Conducting research interviews. Management Research Review,
35(34), 260-271. doi:10.1108/01409171211210154
Ryan, B. L., Brown, J. B., Glazier, R. H., & Hutchison, B. (2016). Examining primary
health care performance through a triple aim lens. Healthcare Policy, 11(3), 19.
Retrieved from http://www.ncbi.nlm.nih.gov
Saleem, J. J., Flanagan, M. E., Russ, A. L., McMullen, C. K., Elli, L., Russell, S.
A.,…Frankel, R. M. (2014). You and me and the computer makes three:
Variations in exam room use of the electronic health record. Journal of the
American Medical Informatics Association, 21(e1), e147-e151.
doi:10.1136/amiajnl-2013-002189
Sandberg, S. F., Erikson, C., Owen, R., Vickery, K. D., Shimotsu, S. T., Linzer,
M.,…DeCubellis, J. (2014). Hennepin health: A safety-net accountable care
organization for the expanded Medicaid population. Health Affairs, 33(11), 1975-
84. doi:10.1377/hlthaff.2014.0648
Scholz, J. (2015). Finding the research questions for care coordination of older adults.
Creative Nursing, 21(1), 21-25. doi:10.1891/1078-4535.21.1.21

114
Schrems B. (2014). Informed consent, vulnerability and the risks of group-specific
attribution. Nursing Ethics, 21(7), 829-843. doi:10.1177/0969733013518448
Schuller, K. A., Kash, B. A., Edwardson, N., & Gamm, L. D. (2013). Enabling and
disabling factors in implementation of studer group’s evidence-based leadership
initiative: A qualitative case study. Journal of Communication in Healthcare,
6(2), 90-99. doi:10.1179/1753807613Y.0000000033
Schultz, E. M., Pineda, N., Lonhart, J., Davies, S. M., & McDonald, K. M. (2013). A
systematic review of the care coordination measurement landscape. BMC Health
Services Research, 13(1), 119. doi:10.1186/1472-6963-13-119
Segal, M., Rollins, E., Hodges, K., & Roozeboom, M. (2014). Medicare-Medicaid
eligible beneficiaries and potentially avoidable hospitalizations. Medicare and
Medicaid Research Review, 4(1), E1-E13. doi:10.5600/mmrr.004.01.b01
Seidman, I. (2012). Interviewing as qualitative research: A guide for researchers in
education and the social sciences. New York, NY: Teachers College Press.
Shaw, F. E., Asomugha, C. N., Conway, P. H., & Rein, A. S. (2014). The patient
protection and affordable care act: Opportunities for prevention and public health.
The Lancet, 384(9937), 75-82. doi:10.1016/s0140-6736(14)60259-2
Shrank, W. H. (2017). Primary care practice transformation and the rise of consumerism.
Journal of General Internal Medicine, 32(4), 387-391. doi:10.1007/s11606-016-
3946-1
Sommers, B. D., Buchmueller, T., Decker, S. L., Carey, C., & Kronick, R. (2013). The
Affordable Care Act has led to significant gains in health insurance and access to

115
care for young adults. Health Affairs, 32(1), 165-74.
doi:10.1377/hlthaff.2012.0552
Song, P. H., McAlearney, A., Robbins, J., & McCullough, J. S. (2011). Exploring the
business case for ambulatory electronic health record system adoption. Journal of
Healthcare Management, 56(3), 169-180. Retrieved from
https://www.ache.org/pubs/jhm/jhm_index.cfm
Stake, R. E. (2010). Qualitative research: Studying how things work. New York, NY:
Guilford Press.
Storkholm, M. H., Mazzocato, P., Savage, M., & Savage, C. (2017). Money’s not on my
mind: A qualitative study of how staff and managers understand health care’s
triple aim. BMC Health Services Research, 17(1), 98. doi:10.1186/s12913-017-
2052-3
Strong, J., Hanson, C. L., Magnusson, B., & Neiger, B. (2015). Health education
specialists’ knowledge, attitudes, and perceptions of the patient protection and
affordable care act. Health Promotion Practice, 17(2).
doi:10.1177/1524839915599360
Tang, L., Gallagher, C. C., & Bie, B. (2015). Corporate social responsibility
communication through corporate websites: A comparison of leading corporations
in the United States and China. Journal of Business Communication, 52(2), 205-
227. doi:10.1177/2329488414525443

116
Taylor, L. A., Tan, A. X., Coyle, C. E., Ndumele, C., Rogan, E., Canavan, M.,…Bradley,
E. H. (2016). Leveraging the social determinants of health: What works. PLoS
ONE, 11(8). doi:10.1371/journal.pone.0160217
Teut, M., & Linde, K. (2013). Scientific case research in complementary and alternative
medicine: A review. Complementary Therapies in Medicine, 21(4), 388-395.
doi:10.1016/j.ctim.2013.04.006
Thomas, E., & Magilvy, J. K. (2011). Qualitative rigor or research validity in qualitative
research. Journal for Specialists in Pediatric Nursing, 16(2), 151-155.
doi:10.1111/j.1744-6155.2011.00283.x
Thomas, J. R., Nelson, J. K., & Silverman, S. J. (2010). Research methods in physical
activity. Champaign, IL: Human Kinetics.
Tong, A., & Dew, M. A. (2016). Qualitative research in transplantation: Ensuring
relevance and rigor. Transplantation, 100(4), 710-712.
doi:10.1097/TP.0000000000001117
Tricco, A. C., Antony, J., Ivers, N. M., Ashoor, H. M., Khan, P. A., Blondal, E.,…Straus,
S. E. (2014). Effectiveness of quality improvement strategies for coordination of
care to reduce use of health care services: A systematic review and meta-analysis.
Canadian Medical Association Journal, 186(15), E568-78.
doi:10.1503/cmaj.140289
Tufford, L., & Newman, P. (2012). Bracketing in qualitative research. Qualitative Social
Work, 11(1), 80-96. doi:10.1177/1473325010368316

117
Tuohy, D., Cooney, A., Dowling, M., Murphy, K., & Sixsmith, J. (2013). An overview of
interpretive phenomenology as a research methodology. Nurse Researcher, 20(6),
17-20. doi:10.7748/nr2013.07.20.6.17.e315
Vaismoradi, M., Turunen, H., & Bondas, T. (2013). Content analysis and thematic
analysis: Implications for conducting a qualitative descriptive study. Nursing &
Health Sciences, 15(3), 398-405. doi:10.1111/nhs.12048
Verdier, J., Streeter, S., Chelminsky, D., & Nysenbaum, J. (2014). Improving
coordination of home health services and durable medical equipment for
Medicare-Medicaid enrollees in the financial alignment Initiative. (Report No.
ac51ab2dfe204a928d3967cb3116f203). Retrieved from http://www.mathematica-
mpr.com
Verhaegh, K. J., MacNeil-Vroomen, J., Eslami, S., Geerlings, S., de Rooij, S., &
Buurman, B. M. (2014). Transitional care interventions prevent hospital
readmissions for adults with chronic illnesses. Health Affairs, 33(9), 1531-1539.
doi:10.1377/hlthaff.2014.0160
Vetter, T. R., Boudreaux, A. M., Jones, K. A., Hunter Jr, J. M., & Pittet, J. F. (2014). The
perioperative surgical home: How anesthesiology can collaboratively achieve and
leverage the triple aim in health care. Anesthesia & Analgesia, 118(5), 1131-1136.
doi:10.1213/ane.0000000000000228
Vipperla, K., Papachristou, G. I., Easler, J., Muddana, V., Slivka, A., Whitcomb, D. C., &
Yadav, D. (2014). Risk of and factors associated with readmission after a sentinel

118
attack of acute pancreatitis. Clinical Gastroenterology and Hepatology, 12(11),
1911-1919. doi:10.1016/j.cgh.2014.04.035
Wahyuni, D. (2012). The research design maze: Understanding paradigms, cases,
methods, and methodologies. Journal of Applied Management Accounting
Research, 10(1), 69-80. Retrieved from http://www.cmawebline.org
Ward, D. J., Furber, C., Tierney, S., & Swallow, V. (2013). Using framework analysis in
nursing research: A worked example. Journal of Advanced Nursing, 69(11),
2423-2431. doi:10.1111/jan.12127
Watson, T. (2012). Making organisational ethnography. Journal of Organizational
Ethnography, 1(1), 15-22. doi:10.1108/20466741211220615
Whiteman, G., Walker, B., & Perego, P. (2013). Planetary boundaries: Ecological
foundations for corporate sustainability. Journal of Management Studies, 50(2),
307-336. doi:10.1111/j.1467-6486.2012.01073.x
Whittington, J. W., Nolan, K., Lewis, N., & Torres, T. (2015). Pursuing the triple aim:
The first 7 years. The Milbank Quarterly, 93(2), 263-300. doi:10.1111/1468-
0009.12122
Wilf-Miron, R., Bolutin, A., Gordon, N., Porath, A., & Peled, R. (2014). The association
between improved quality diabetes indicators, health outcomes and costs:
Towards constructing a business case for quality of diabetes care. BMC Endocrine
Disorders, 14(1), 81-95. doi:10.1186/1472-6823-14-92
Wisdom, J. P., Cavaleri, M. A., Onwuegbuzie, A. J., & Green, C. A. (2012).
Methodological reporting in qualitative, quantitative, and mixed methods health

119
services research articles. Health Services Research, 47(2), 721-745.
doi:10.1111/j.1475-6773.2011.01344.x
Wolcott, H. F. (1999). Ethnography: A way of seeing. Lanham, MD: Altamira.
Wolfswinkel, J. F., Furtmueller, E., & Wilderom, C. P. (2013). Using grounded theory as
a method for rigorously reviewing literature. European Journal of Information
Systems, 22(1), 45-55. doi:10.1057/ejis.2011.51
Wright, D. (2012). Redesigning informed consent tools for specific research. Technical
Communication Quarterly, 21(2), 145-167. doi:10.1080/10572252.2012.641432
Wysocki, A., Kane, R. L., Golberstein, E., Dowd, B., Lum, T., & Shippee, T. (2014). The
association between long-term care setting and potentially preventable
hospitalizations among older dual eligibles. Health Services Research, 49(3), 778-
797. doi:10.1111/1475-6773.121mk68
Xing, J., Goehring, C., & Mancuso, D. (2015). Care coordination program for
Washington state Medicaid enrollees reduced inpatient hospital costs. Health
Affairs, 34(4), 653-661. doi:10.1377/hlthaff.2014.0655
Xu, P., Burgess, J. J., Cabral, H., Soria-Saucedo, R., & Kazis, L. E. (2015). Relationships
between Medicare Advantage contract characteristics and quality-of-care ratings:
An observational analysis of Medicare Advantage star ratings. Annals of Internal
Medicine, 162(5), 353-358. doi:10.7326/M14-0332
Yilmaz, K. (2013). Comparison of quantitative and qualitative research traditions:
Epistemological, theoretical, and methodological differences. European Journal
of Education, 48(2), 311-325. doi:10.1111/ejed.12014

120
Yin, R. K. (2014). Case study research: Design and methods. Thousand Oaks, CA: Sage
Publications.
Zainulbhai, S., Goldberg, L., Ng, W., & Montgomery, A. (2014). Assessing care
integration for dual-eligible beneficiaries: A review of quality measures chosen by
states in the financial alignment initiative. SSRN Journal.
doi:10.2139/ssrn.2417416
Zamawe, F. C. (2015). The implication of using NVivo software in qualitative data
analysis: Evidence-based reflections. Malawi Medical Journal, 27(1), 13-15.
doi:10.4314/mmj.v27i1.4
Zangerle, C. M., Harris, D. A., Rimmasch, H., & Randazzo, G. (2016). From volume-to
value-based care: Leading population health initiatives. Nurse Leader, 14(5), 318-
322. doi:10.1016/j.mnl.2016.06.003
Zink, T., Kralewski, J., & Dowd, B. (2017). The transition of primary care group
practices to next generation models: Satisfaction of staff, clinicians, and patients.
The Journal of the American Board of Family Medicine, 30(1), 16-24.
doi:10.3122/jabfm.2017.01.160118

