


1
Chapter 1: Introduction to the Study
Introduction and Background
The Department of Defense (DoD) is responsible for overseeing the Military
Health System (MHS), the means for providing care to military members, retirees, and
eligible family members. The MHS is the primary source of rendering health care in
military treatment facilities (direct care system), which is augmented by care provided
under the Civilian Health and Medical Program of the Uniformed Service
(CHAMPUS)/TRICARE in the private sector (purchased care) in the United States and
overseas. Outside the United States and its territories, except for the District of Columbia,
CHAMPUS/TRICARE is referred to the TRICARE Overseas Program (TOP), which is
the same CHAMPUS/TRICARE program administered in the United States, with the
overseas cultural differences and nuisances for every country being taken into
consideration.
The DoD is concerned with escalating health care costs throughout the MHS. In
general, the rising costs of health care can be attributed to factors including advanced
technology, people living longer, fraud and abuse, inflation, changes in physicians’
philosophy in treating their patients, and malpractice suits. This research focused on the
exorbitant rise in health care costs in the Philippines. According to Scott (2006), the
excessive increase in health care costs in the Philippines caught the attention of the
DoD’s Office of the Inspector General (DoDIG), prompting an investigation into
improper payments to providers and third-party billing agencies and waiving of
beneficiaries’ deductibles and cost shares. The DoDIG found that the Defense Health

2
Agency (DHA), formerly TRICARE Management Activity (TMA), paid $2.87 million in
fiscal year (FY) 1988 and $64.19 million in FY 2003 for health care in the Philippines
(Scott, 2006). These amounts reflected a 2,135% rise in health care costs over a 6-year
period to a population that had remained relatively stable throughout 5 plus years (Scott,
2006). The DoDIG recommended that DHA implement provisions of accountability for
claims submitted by providers and third-party billing agencies that submit claims on
behalf of the providers and initiate steps toward ensuring that providers do not waive the
cost shares and deductibles of beneficiaries (Scott, 2006). The DoDIG conducted an audit
to examine inaccurate reimbursements of TRICARE claims and the necessity for the
establishment of negotiated rates for health care services rendered overseas (Prinzbach,
2008).
The DoDIG also conducted an audit from July 2009 through June 2011 to assess
the certification of Philippine providers who rendered health care to military retirees and
their families and the process for adjudicating the claims associated with health care
(Carey, 2011). The audit found that the TOP contractor who was responsible for provider
certification failed to “provide adequate documentation to support 28 of 63 certifications
of medical providers,” and the overseas claims processor failed to verify the addresses of
TRICARE beneficiaries before mailing reimbursement checks (Carey, 2011). The
DoDIG reported that beneficiaries were in jeopardy of receiving care from providers who
were not certified and licensed and that beneficiaries did not receive reimbursement from
TRICARE because their addresses were never confirmed (Carey, 2011).

3
The DoDIG audits recommended several areas in which the DoD could reduce the
cost of health care in the Philippines. As a result, the DHA implemented several
administrative controls in the Philippines that lowered the cost of health care somewhat,
but other cost containment measures are still necessary. Therefore, the DHA devised a
plan to implement the DoD TRICARE Philippine Demonstration Project (Philippine
Demonstration) as a cost containment measure and fraud deterrent.
The following sections include the problem statement, research questions and
associated hypotheses, the theoretical basis for the study, the nature and scope of the
study, and its assumptions, delimitations, and limitations. The chapter concludes with a
section on the professional and social implications of the study that addresses how the
study contributes to the delivery of an alternative health care model and social change.
Problem Statement
TMA (2008a) identified a major concern in the Philippines with rising health care
costs. The Philippines has a reputation for ubiquitous health care fraud within TRICARE,
so the DHA of the DoD implemented administrative controls to deter fraud in the
Philippines (TMA, 2008a). In 2013, the DHA implemented the DoD TRICARE
Philippine Demonstration because the administrative controls were not enough to deter
fraud and decrease health care costs.
The purpose of this quantitative cross-sectional research study was to determine
the efficacy and acceptability of a different method to deliver health care to increase
access to health care and decrease out-of-pocket costs while maintaining quality of care

4
for TOP Standard beneficiaries who receive health care under the Philippine
Demonstration.
Gaps in the Literature
Scholars have addressed country-specific health systems, rising medical costs,
cost containment strategies, reimbursement methods, and fraudulent claims submissions
in extensive literature writings. I am not aware of any literature with controlled studies
that integrates the MHS with foreign health care systems testing a different method of
providing health care. The Philippine Demonstration is the first time the DoD has tested
an alternative method of providing care in a foreign country. The DoD conducted a
demonstration testing an alternative method of delivering health care to beneficiaries and
active service members in the 1990s in 11 states under the CHAMPUS Reform Initiative
during the managed care era (Anderson, Hosek, & Bloomfield, 1994). This
demonstration resulted in the addition of a health maintenance organization option and a
preferred provider organization (PPO) option to CHAMPUS.
Purpose of the Study
The cost of health care continued to rise in the Philippines, while the number of
TRICARE beneficiaries has remained the same. According to TMA (2008a), the
Philippines is known for its widespread health care fraud against the TRICARE program.
The DHA implemented administrative controls such as proof of payment, prepayment
review, boots-on-the-ground validation and certification, a government-directed foreign-
fee schedule, and attestation, but these controls alone have not been sufficient to address
the problem (TMA, 2008a). As an alternative method of health care delivery, the DoD

5
TRICARE Philippine Demonstration was conceptualized as a resolution to provide
beneficiaries using the TRICARE Standard option access to quality care as well as to
control health care costs without jeopardizing access to quality care.
Therefore, the purpose of this quantitative cross-sectional research study was to
determine the accessibility and acceptability of health care received under the Philippine
Demonstration for TOP Standard by beneficiaries, retirees, family members, and
TRICARE for Life beneficiaries who reside in the Philippines.
Nature of the Study
This study was of a quantitative nature. I used the quantitative research design to
address questions regarding access to care, cost, and quality of care for the TRICARE
Standard population who reside in the Philippines and receive care in designated
Demonstration areas (Creswell, 2009). Essentially, I adopted a postpositivist view (see
Creswell, 2009) using Andersen’s (1995) behavioral model of health services use and
used Donabedian’s (1990) quality model to assess patient experience and satisfaction.
Research Question and Hypotheses
I derived the following research questions (RQs) from the DoD TRICARE
Philippine Demonstration Beneficiary Satisfaction Survey:
RQ1: How has the Demonstration affected the beneficiaries’ financial burdens
and confidence that their health care needs will be met?
H01a: There is no statistically significant relationship between financial
burdens and satisfaction with the Demonstration overall.

6
Ha1a: There is a statistically significant relationship between financial burdens
and satisfaction with the Demonstration overall.
H01b: There is no statistically significant relationship between financial
burdens and confidence that health care needs will be met.
Ha1b: There is a statistically significant relationship between financial burdens
and confidence that health care needs will be met.
RQ2: What is the relationship between gender, age, and health care finder
functionality for accessing quality health care under the Demonstration in Metro
Manila, Cavite City, Cavite, and Iloilo City, Iloilo?
H02a: There is no statistically significant relationship between gender, age,
and health care finder functionality access to quality health care in Metro
Manila, Cavite City, Cavite, and Iloilo City, Iloilo.
Ha2a: There is a statistically significant relationship between gender, age, and
health care finder functionality access to health care in Metro Manila, Cavite
City, Cavite, and Iloilo City, Iloilo.
RQ3: What is the relationship between a closed network, actual beneficiary out-
of-pocket cost, and quality health care in Demonstration areas?
H03a: There is no statistically significant relationship between actual
beneficiary cost and a closed provider network.
Ho3a: There is a statistically significant relationship between actual
beneficiary out-of-pocket cost and a closed provider network.

7
H03b: There is no statistically significant relationship between quality health
care and a closed provider network.
Ha3b: There is a statistically significant relationship between quality health
care and a closed provider network.
Beneficiaries’ Actual Out-of-Pocket Costs
In order to determine if beneficiaries out of pocket costs decreased, it is
imperative to conduct an analysis of their out of pocket costs for calendar years 2011,
2012, 2013, 2014, and 2015 in Metro Manila, Cavite City, Cavite, and Iloilo City, Iloilo
decrease or increase. Prior to the Philippine Demonstration, beneficiaries paid a
deductible and cost share plus balancing billing. After the implementation of the
Philippine Demonstration, beneficiaries paid a deductible and cost share. It is my
assumption that beneficiaries’ overall out-of-pocket costs would increase initially
because greater than half the TRICARE beneficiaries were not using the TRICARE
benefit. As more beneficiaries use the TRICARE benefit and receive care from approved
demonstration providers, the cost should eventually decrease.
Theoretical Base
As a theoretical framework, I used Andersen’s behavioral model of health
services use and Donabedian’s quality model are used to explain the study results. The
goal of Andersen’s (1995) model was “to provide measures for access to medical care”
(p. 4) to include potential, realized, equitable, and inequitable access. Andersen enhanced
the model to include measures important for health policy and reform. Andersen’s model
in the third phase measures for effective access as shown by improved health status

8
through use or beneficiary satisfaction. Efficient access is based on health status and
increased satisfaction in relation to the consumption of health care (Andersen, 1995).
Donabedian’s (1980) quality assessment of health care was based on the experience of
the patient. Donabedian’s (1980) quality assessment model looks at how the patient
defines quality based on his or her values and expectations.
The theoretical foundation for this study, presented in depth in Chapter 2, was the
Andersen’s behavioral model access utilization and Donabedian’s quality assessment. For
this study, access was defined as the entry point when a patient enters the health system.
Operational definitions for other concepts used in this study are listed in the following
section.
I present a more detailed description of the theoretical framework as well as the
conceptual model that grounds this study in Chapter 2.
Definition of Terms
Definitions of terms used in this study were as follows:
Access: The point of entry where a patient enters the health care system.
Approved Demonstration provider: A provider in the Philippines who has agreed
to participate in the DoD TRICARE Philippine Demonstration. This provider has agreed
to accept the TRICARE-allowed amount that includes the beneficiary cost share and
deductible and submit claims for the TRICARE beneficiaries for medical services
provided. The provider has also agreed to meet the terms of on-site verification,
certification, and credentialing according to TRICARE regulations and policies. An

9
approved Demonstration provider may opt to require TRICARE beneficiaries to pay their
deductible and cost shares up front for services provided.
Certified Philippines provider: A provider who has met the on-site verification,
certification, and credentialing requirements. This provider has not agreed to accept the
TRICARE allowed amount that includes the beneficiary cost share and deductible or to
submit claims for TRICARE beneficiaries for medical services provided. This provider
can require TRICARE beneficiaries to pay the entire bill in full up front for services
provided.
Civilian Health and Medical Program of the Uniformed Service (CHAMPUS):
Medical program established to provide care to family members and retired military
members in the private sector.
Health care fraud: Providers intentionally bill services at a higher level
suitable for the services rendered to the patient.
Power purchasing parity: Calculating the exchange rate of currency for different
countries in order to purchase the same goods in one country at the same rate in another
country.
Quality of health care: Consists of structure, process, and outcome as defined by
Donabedian (1966).
TRICARE beneficiary: A military service member, retired service member, or
eligible family members of the military or retired service members. For the purposes of
the DoD TRICARE Philippine Demonstration, TRICARE beneficiaries were retired

10
service members and eligible family members of the military and retired service members
living in the Philippines.
TRICARE program: The DoD managed care program that allows for competitive
selection of contractors who are willing to take financial risks for health care delivery
under CHAMPUS (TMA, 2009). The implementation of TRICARE was an enhancement
to CHAMPUS introducing TRICARE Prime (DoD health maintenance option),
TRICARE Extra (preferred provider option), and TRICARE Standard (basic CHAMPUS
fee-for-service).
TOP: The TRICARE health care program administered overseas and in the U.S.
territories, except for the District of Columbia. There is one option available overseas for
nonactive service beneficiaries, the TOP Standard option.
Assumptions
TRICARE Standard beneficiaries residing in the Philippines compose a small
segment of the Filipino population accessing health care. The DoD TRICARE Philippine
Demonstration hinges on providers in the civilian sector joining a closed network of
providers to provide care to TRICARE Standard beneficiaries and accepting what
TRICARE allows as payment in full. I assumed that some TRICARE beneficiaries
residing in the Philippines would be resistant to receiving care under the Demonstration,
while other beneficiaries would welcome the alternative method of delivering health care
for a decrease in out-of-pocket costs and an increase in access to quality health care. I
expected that age and gender would have an impact on the health care functionality.

11
Limitations
The accuracy of the CHAMPUS/TRICARE beneficiary contact information was a
major limitation for the Beneficiary Satisfaction Survey. For example, a beneficiary may
not have updated their address or telephone number in the Defense Enrollment Eligibility
Reporting System (DEERS), the official system of record for CHAMPUS/TRICARE
beneficiaries. These beneficiaries input their personal contact information, such as
mailing address, telephone number, and e-mail address (this is not a required field) in
DEERS. Like any database, the information is only as good as the data that goes into the
database. If beneficiaries did not update their information, their chances for participating
in the survey were decreased. Outreach to the beneficiaries in the Philippines informing
them to update their personal information via the DHA’s Web site or the TOP
contractor’s Web site should have minimized this limitation.
The country code listed in DEERS for Philippines addresses is “PHL”; however,
the country code listed for an Army Post Office or Fleet Post Office (APO/FPO) address
in the Philippines is “US.” The “US” country code automatically excluded a legitimate
APO/FPO address in the Philippines, thus eliminating potential respondents for the
survey. The inclusion of the zip code for the APO/FPO address as a data element should
have resolved this limitation. Although Tagalog is the native language in the Philippines,
English is a familiar language in the Philippines. Some beneficiaries who do not speak
English can opt to have someone in the household translate. If beneficiaries required a
translator, the interviewer should have required the beneficiary to authorize the
interviewer to speak with the individual in the household as a translator. The interviewer

12
should have documented the authorization to show there was no breach of the Health
Insurance Portability and Accountability Act of 1996 (HIPAA). There is a possibility in
which beneficiaries with one e-mail address per household may not have received a
survey to avoid violating HIPAA. The only way the beneficiary could receive a survey
via e-mail was to notify the DHA official appointed to oversee this survey and provide
authorization to send a survey via e-mail if the beneficiary met the criteria to participate
in this survey.
Telecommunications barriers exist in the Philippines because some beneficiaries
may only have a mobile telephone. In cases such as this, the beneficiary may not have
answered the telephone or had the telephone set up not to accept incoming calls because
the call would use the minutes on the telephone plan. If the beneficiary had a usable e-
mail address, the survey could have been sent via e-mail. There were other barriers, such
as an incorrect telephone number in DEERS that could have been be remedied by the
beneficiary updating their contact information in DEERS.
Delimitations
This study was delimited to TRICARE Standard beneficiaries who lived in the
Philippines and received health care from approved Demonstration providers in
designated Demonstration areas from January 1, 2013, through December 31, 2015. The
purpose of this study was to evaluate the patient’s experience to determine the efficacy
and acceptability of the Philippine Demonstration, focusing on outcome measures for
access to quality of health care and beneficiaries’ financial burdens. I used secondary data
from a Beneficiary Satisfaction Survey directed to respondents who received health care

13
during all phases of the Demonstration. This research confirmed if the DoD met its
objective, decreasing out-of-pocket costs for beneficiaries while ensuring that the
beneficiaries maintained access to quality health care in the Philippines.
Significance of the Study
According to Schoen et al. (2010), the health insurance design affected access,
cost, and experience of care in various countries. The Philippine Demonstration will
allow the DoD to determine whether it is possible to control costs, reduce aberrant claims
activity, and eliminate balance billing issues while providing high-quality, safe, and
effective health care to TRICARE Standard Overseas beneficiaries who reside in the
Philippines and receive care in designated Demonstration areas (TMA, 2008). The
alternative method will change the reimbursement methodology, reducing out-of-pocket
costs and eliminating payment in full of services up front, thus alleviating financial
burdens for beneficiaries.
The Philippine Demonstration would have a major impact on health care delivery
for TRICARE Standard beneficiaries residing in the Philippines and providers rendering
services to these beneficiaries. The engagement of cultural and economic differences in
two very distinct health care systems, the MHS and the Philippines health care system,
would merge, creating social change.
Professional Application
The DoD will assess the efficiency and acceptability of the Demonstration during
and at the end of the 3-year Demonstration. If it is successful, there is a possibility that a
closed network of preferred providers may be implemented throughout the Philippines. A

14
closed network of preferred providers could become the premier health care delivery
model for TRICARE Standard beneficiaries who receive health care overseas.
Access to providers in the Philippines was never a concern because TRICARE
Standard beneficiaries had the option to see any TRICARE certified provider. The
implementation of a closed network of preferred providers guarantees access to quality
providers who are committed to providing safe, quality health care to TRICARE
beneficiaries at a lower cost. Health care costs could eventually decrease due to the
acceptability of the fee schedule by providers versus the DHA paying billed charges in
various countries. Furthermore, decreasing the number of providers should result in better
oversight of health care that could eventually lead to a decline in fraud.
Philippine Demonstration Blueprint
The DHA established specific criteria to use a phased approach for launching the
Philippine Demonstration in designated areas. The TOP contractor who administers the
TRICARE program overseas was responsible for developing a closed network of
physicians, hospitals, and other practitioners that could provide quality care to TRICARE
beneficiaries (TMA, 2008a). The TOP contractor was responsible for determining the
ratio of medical providers and specialties based on the population of TRICARE Standard
beneficiaries (TMA, 2008a). The TOP contractor selected a limited number of providers
who met the credentialing and licensing criteria imposed by Philippine law and U.S. law.
The selection criteria excluded providers who were on prepayment review (TMA,
2008a).

15
The TRICARE medical benefit under the Philippine Demonstration did not
change from the original TRICARE medical benefit (TMA, 2008a). The TOP contractor
is responsible for utilization management, case management, and quality management for
beneficiaries receiving care under the Philippine Demonstration (TMA, 2008a). The TOP
contractor is also responsible for functioning as health care finder to assist beneficiaries
in locating approved Demonstration providers (TMA, 2008a). The TRICARE Standard
beneficiary is still responsible for obtaining preauthorizations for specific care as outlined
in the TRICARE Policy Manual (TMA, 2008a). Although access to care standards is not
part of the TRICARE Standard option, the approved Demonstration providers are
required to meet TRICARE access standards for appointments. Beneficiaries seeking
appointments for urgent care should be seen the same day, for routine care within 7 days,
and for specialty care within 30 days (TMA, 2008a).
The reimbursement method changed for providers under the Philippine
Demonstration. The change in reimbursement required providers to accept the
government-directed foreign-fee schedule as payment in full to eliminate balance billing
for TRICARE beneficiaries (TMA, 2008a). The approved Demonstration provider can
request the TRICARE Standard beneficiary to pay their cost share and annual deductible
at the time the medical services are provided. Beneficiaries who receive care in
designated Demonstration areas must receive care from approved Demonstration
providers or obtain a waiver to see a certified provider to avoid paying 100% of the cost
for covered services (TMA, 2008a).

16
Implications for Positive Social Change
The Philippine Demonstration would have a major influence on health care
delivery for TRICARE Standard beneficiaries residing in the Philippines and providers
rendering services to those beneficiaries. The blending of the MHS and the Philippines
health care system, two very distinct health care systems, would create positive social
change.
The use of the foreign fee schedule reimbursement methodology using the
purchasing power parity conversion factor allows the DoD to purchase the same amount
and type of health care services in the Philippines of equal value. Before the Philippine
Demonstration, the DoD reimbursed medical care based on the foreign-fee schedule, but
the providers were not required to accept the foreign-fee schedule as payment in full. To
be an approved provider under the Philippine Demonstration, the provider must agree to
accept the TRICARE maximum allowable charge based on the foreign fee schedule as
payment in full (TRICARE Operations Manual, 2008a). The financial burden would be
decreased for the TRICARE Standard beneficiary because they would be liable only for
the annual deductible, individual or family, and cost shares and balance billing would be
eliminated under the Philippine Demonstration. In some instances, the beneficiary would
not be burdened with having to make upfront payments before hospital admissions or
high-cost outpatient services.
There should be a significant reduction in unusual claims activity. A provider who
desires to become an approved Demonstration provider must not be on prepayment
review, agree to accept the foreign-fee schedule, agree to file the claim on behalf of the

17
beneficiary, and agree to list their name in the approved Demonstration provider database
(TRICARE Operations Manual, 2008a). Implementing a PPO model with approved
demonstration providers limits the number of providers so that an appropriate patient to
provider ratio can be obtained using a beneficiary-sizing model. When the pool of
providers is small, the TOP contractor can monitor the billing activities of the providers
more efficiently, decreasing or eliminating fraudulent activities.
If the government determines that it met the expected objectives, there is a
possibility that this alternative method of delivering and reimbursing health care may
become the health care model in other countries for all TRICARE Standard beneficiaries
where accessing safe, quality care is problematic, and the government reimburses billed
charges to health care providers.
Summary and Transition
This chapter presented the major constructs of the study, the RQs, and gaps in the
current literature. Chapter 2 poses major themes from the relevant literature, the
theoretical base of the research, and the methodology for statistical analysis. Chapter 3
provides information regarding the sample, data, independent and dependent variables,
and methodology selected to explore relationships between and within variables. Chapter
4 presents the statistical analysis of data and key findings. Chapter 5 concludes with a
discussion of the implications of the findings for access to high-quality care in the
Philippines while containing health care costs.

18
Chapter 2: Literature Review
Introduction
The purpose of this literature review is to assess articles on access, quality care,
and cost containment mechanisms incorporating the health system for one country
(United States) with another country’s health system (Philippines) to determine if an
alternative method for providing medical care would be efficient and acceptable.
Search Strategy
A comprehensive search strategy was used to locate relevant articles related to
access to health care, health care financing, and quality of care based on the experience of
patients. Multiple databases were used to locate published studies that were conducted in
the literature on health services, health care fraud, quality, political science, business, and
economics for the years 1966–2015. Databases included Academic Premier, CINAHL
Plus, Emerald, OVID, ProQuest, PubMed, SAGE, ScienceDirect, Thoreau, and Google
Scholar. Keywords used included access to care, quality of care, patient experience,
health care fraud, managed care, CHAMPUS, TRICARE, health care reimbursement,
Philippine health care, and patient satisfaction. Any recent research that used patient
experience, quality of care, and access to care theories to explain patient satisfaction were
included. Only articles that were peer reviewed and appeared in scholarly journals were
included.
Theoretical Frameworks: Access to Health Services and Quality Health Care
Andersen’s behavioral model for health care laid the foundation for assessing
health care access and utilization. The initial framework, behavior families’ use health

19
services, has undergone five modifications, wherein scholars and Andersen have made
modifications to fit the assessment of health care. During this period, cost containment
was not an issue. Rather, the model focused on situations that enabled or obstructed the
utilization of health care (Andersen, 1995). The purpose of this theoretical framework is
to evaluate the effectiveness of the Philippine Demonstration’s impact on health care
delivery access using a PPO.
Andersen’s Behavior Families’ Use of Health Services
The behavior families’ use health services model was developed in the 1960s to
(a) determine the reason a family unit would access medical care, (b) construct a
definition for equitable access as well as determine the variables to measure equitable
access, and (c) incorporate the policy aspect for equitable access to care (Andersen, 1974,
1995, 2008). Andersen (1974, 1995, 2008) posited that a family’s demographic and
socioeconomic factors and health policy could elucidate the use of medical care.
Furthermore, Andersen determined that the family unit’s head of household gender, race,
ethnicity, education, and beliefs about health illuminate the use of seeking care (Aday &
Awe, 1997; Andersen, 1974, 1995, 2008). Health care policy, insurance, income, and
availability of facilities either enable or obstruct the use of care by the family (Andersen,
1974, 2008). The family unit’s environment dictates the need for medical care, for
example, the location where the family lives and their health status (Aday & Awe, 1997;
Andersen, 1974, 1995, 2008). Since the conception of Andersen’s original model, several
iterations have taken place to build upon the behavioral model improving its usefulness.

20
Phase 2. Andersen and Aday incorporated a health care system because of the
significance of national health policy and resources and organizational structure for
accessing care, and consumer satisfaction as an outcome measure for using the health
system (Aday & Andersen, 1974; Aday & Awe, 1997; Andersen, 1995, 2008). Aday and
Andersen (1974) acknowledged that the use of medical care falls within the scope of
politics for making changes to the health care system, and according to Aday and Awe
(1997), Andersen’s model was the first national survey assessing access to care in the
United States.
Phase 3. Andersen and Newman (1973/2005) integrated societal determinants,
health systems services, individual determinants, and health services utilization in
Andersen’s behavioral model (see also Aday & Awe, 1997). Andersen and Newman
(1973/2005) posited that individual determinants are affected by societal determinants
(technology and norms) and the health services system (resources and organization). The
societal determinants of this model posit that advancement in technology as well as
societal norms and values have affected the use of health services (Andersen & Newman,
1973/2005). For example, the shift in surgical technology has evolved in such a way that
it changed the length of hospital stays patients usually experience for complex surgeries.
Advances in therapeutic medication and the location where patients receive treatment, as
shown in the reduction of mortalities because of infectious disease, and the reduction of
conditions requiring inpatient treatment treated on an outpatient basis are additional
examples of the effects of advancements in technology. The societal norms dictate the

21
financing of health services, and societal values play a role in financing some health
services (Andersen & Newman, 1973/2005).
Andersen and Newman’s (1973/2005) health services system’s components
included resource and organization. The resource element included the dedicated finances
for providing health care and some resources to provide the appropriate provider to
patient ratio. The organization element examined the requirements for individuals to
access medical care and the identification and resolution of barriers interfering with
individuals accessing medical care. The cost of care in the form of out-of-pocket
expenses by individuals, wait time for some specialty treatments, and the different
qualifying conditions (benefits) can delay patients accessing needed medical care.
Andersen and Newman believed that access to health care would increase if patient out-
of-pocket expenses decreased because of public and private insurance, decreased wait
times for medical care, and an increase in the number of conditions (benefits). The
structure element under the organization component is the most complicated element
(Andersen & Newman, 1973/2005). The structure element links to other elements for
accessing care. The process for treating patients after entering the health system includes
evaluating the type of provider first administering care, required ancillary services,
referrals for specialty care, and necessary hospital admissions.
The individual predisposing factor includes sociodemographic factors, whereas
structure (age, gender, past illnesses), social structure (education, cultural factors,
religion), and beliefs (values regarding health, attitudes toward obtaining medical care,
and knowledge of different diseases) dictate the propensity for accessing care (Andersen

22
& Newman, 1973/2005). The individual enabling factor includes family (income, health
insurance coverage, accessibility of care) and community (provider [individual and
facility] to patient ratio, the cost of care, and place of care) components that might affect
utilization of medical care (Andersen & Newman, 1973/2005). The illness level
perceived (disability days away from work or school, symptoms of the individual, health
status of fair, good, or excellent reported by the individual) and evaluated (diagnoses of
illness caused by symptoms) determined the need for medical care (Andersen &
Newman, 1973/2005). According to Andersen and Newman, individual determinants,
predisposing, enabling, and illness level, are important in determining utilization patterns.
The illness level component (perceived and evaluated) under the individual determinant
ranked the highest for the relative importance of use (Andersen & Newman, 1973/2005).
Andersen and Newman (1973/2005) emphasized the health services use
component. The significant factors under the health services use component are type,
purpose, and unit of analysis. The type of health services use is affected by societal
determinants for various providers (individual, facility, and dental) of care. The purpose
of care is broken out into categories of primary care (prevention of illness), secondary
care (treatment of illness), tertiary care (stabilization of chronic conditions), and custodial
care (provides personal needs only). The unit of analysis accounts for contact (initial
contact or number of services during a period of time), volume (number of time patient
accesses medical care and type of provider), and episodic care (specific diagnoses) for the
use of health services (Andersen & Newman, 1973/2005).

23
Andersen (1995) included consumer satisfaction with health status based on the
perspectives of the population and providers as a measurement of health outcomes.
According to Andersen, effective access had been achieved when the population’s health
status or satisfaction with the health care provided improved. Additionally, efficient
access is based on health status and increased satisfaction about the consumption of
health care measures relevant to health policy and reform (Andersen, 1995).
Phase 4. The fourth iteration of the behavioral model of health services use was
modified to show several factors for use of health services and health status (Andersen,
1995). This model indicates that future predisposing, enabling, and need characteristics
have the propensity to be affected by outcomes (Andersen, 1995).
Phase 5. Modernization of Andersen’s current model, the behavioral model of
health services use, incorporated the reasons for the population using medical care
through contextual characteristics and individual characteristics. The components of this
model’s framework consist of contextual characteristics, individual characteristics, health
behaviors, and outcomes (Andersen, Davidson, & Baumeister, 2010). This model
examined contextual characteristics to determine (a) the illnesses that caused the
community to access care, (b) the factors that enabled or obstructed the community’s
access to care, and (c) the circumstances that were noticeable by the patient or provider
that medical care was needed.
Contextual characteristics. The contextual predisposing characteristics
identified the conditions under which care was accessed as demographics, social status,
and beliefs (Andersen et al., 2010). The contextual enabling characteristics are health

24
policies, financial resources, and organization structure in the community. Health policies
at the federal, state, and local levels can affect access to health services. The impact of
federal health policies and international health policies affected access to health services
and the quality of health care for TRICARE Standard beneficiaries in the Philippines.
Financial resources available for purchasing health care, cost of care, method of
reimbursing providers, and health insurance coverage were measured. The structure of
the organization consisted of the number of facilities and providers, a mix of providers to
include the types of services in the community, use management, quality assessment, and
mechanisms for educating purchasers and providers of health care (Andersen et al.,
2010). The contextual need characteristics included measurements of the population
health indicators that are linked to the community but not necessarily linked to the
environment (Andersen et al., 2010). The rate of mortality, morbidity, and disability
conditions are measurements of population health.
Individual characteristics. The individual predisposing characteristics are
demographic, social status, and health beliefs (Andersen et al., 2010). The individual’s
age and gender play a part in the propensity for accessing health services. The social
status of the individual, such as level of education, cultural background, and type of
work, can enable or obstruct individuals’ access to health services. The values, beliefs,
and experiences of individuals with health services can affect their future health services
use.
The mutability of enabling determinants for the family and community factors is
high, whereas the mutability of predisposing determinants for sociodemographics is low,

25
and beliefs are medium (Andersen & Newman, 1973/2005). The distribution of health
services is affected by specific factors that can undergo change. Decision makers, health
care administrators, and political leaders can use health care policy to improve access,
use, and quality.
Andersen’s (1995) behavioral model of health services is a prominent model used
by researchers to assess access to care (Ricketts & Goldsmith, 2005). Andersen’s
behavioral model, initially conceptualized in 1960, focused on policy development for
access to care, reasons associated with families’ consumption of medical care, and on
clarifying and evaluating access to care. Throughout the years, Andersen’s behavioral
model underwent several iterations. Other scholars perfected the second phase of
Andersen’s model in the 1970s, introducing the health care system and national health
policy and consumer satisfaction and use as important indicators for measuring access to
care. Andersen perfected the third phase of the behavioral model, focusing on
individuals, measures for effective access as shown by improved health status and
improved beneficiary satisfaction, and efficient access based on health status and
increased satisfaction in relation to the consumption of health care measures, which are
important for health policy and reform. Karikari-Martin (2011) asserted there is no
consistency between the different theoretical frameworks for measuring access. Karikari-
Martin examined Penchansky’s model, which measured availability, accessibility,
accommodation, affordability, and acceptability, whereas the Institute of Medicine model
measured access impediments, use of services, and use of mediators, and the behavioral
model of health measured the influence of community-level and individual-level

26
characteristics on access. Andersen’s behavioral model of health services was best suited
for this research.
Donabedian’s Quality of Health Care
Donabedian (1980, 2003) pointed out that before assessing the quality of care,
there must be a shared understanding of what constitutes quality. Donabedian found
defining quality in health care to be challenging but necessary. Donabedian divided
quality in health care into two distinct elements: (a) technical management, which is
science and technology, and (b) interpersonal management, which is the application of
science and technology. Donabedian (1980) added amenities as the third element of
quality in health care, which could be an aspect connected to interpersonal management.
The innovation of science and technology coupled with health professionals using the
knowledge derived from science and technology to take care of patients produces
attributes of quality in health care.
The attributes of quality in health care are efficacy, effectiveness, efficiency,
optimality, acceptability, legitimacy, and equity (Donabedian 1980, 2003). Quality in
health care can be defined “as the degree to which health services for individuals and
populations increase the likelihood of desired health outcomes and are consistent with
current professional knowledge” (Institute of Medicine, 1990, p. 44).
Structure, process, and outcome. Donabedian explained health care quality
through the concept of structure, process, and outcome. Donabedian’s (1980, 2003)
quality theory uses structure, process, and outcome to assess the quality of care.
Donabedian (2003) made it clear that “structure, process, and outcome are not attributes

27
of quality” but are three approaches used to presume “whether quality is good or not” (p.
47). According to Donabedian (1980, 1988, 2003), a functional relationship must exist
between structure, process, and outcome to make any presumptions regarding quality.
Structure depicted a place of health care delivery, human resources,
reimbursement methodology, and instrumentality to perform health services. Process
depicted the actions of patients to access health care and the actions of health
professionals to provide health care. Outcome depicted “the effects of care on the health
status of patients and populations” (Donabedian, 1988, p. 1745). Donabedian’s (1980,
1988, 2003) quality model shows the importance of the existence of a functional
relationship between structure and process as well as process and outcome to evaluate the
quality of health care.
Health Care in the United States
The U.S. health care system is a complex, mixed system with public- and private-
sector health schemes. The public sector scheme is composed of health systems that are
managed by the government. The Bismarck model, a social insurance system, created in
1883, and the Beveridge model, a universal system, formed in 1946, are the basis for
Medicare, a federal program established in 1965 (Kovner & Knickman, 2011).
Employees and employers contribute to Medicare. Medicare was created to provide
medical care to individuals who turned 65 and individuals with disabilities regardless of
age. The Balanced Budget Act, amended in 1967, created Medicaid and the Children’s
Health Insurance Program, extending access to care for children whose parents did not
have the means to buy care in the private sector (Longest, 2006). The federal and state

28
governments fund Medicaid. The U.S. Veterans Health Administration and DoD health
systems are based on the Beveridge model and are funded by taxes, copayments, and cost
shares from eligible beneficiaries.
Health expenditure 2011. The United States is classified as a high-income
country with a population of 316,094,000 (World Population Statistics, 2013).
Expenditures for medical care in the United States are constantly rising in the public and
private sectors. In 2010, the United States paid $2.7 trillion for health care, and the total
national health expenditure capped at 17.9% of the gross domestic product from 2009
through 2011, with a spending growth rate of 3.9% (Centers for Medicare and Medicaid
Services, 2013). The cost of health care will outgrow the gross domestic product, and if
not contained, health care costs will use up a significant portion of the gross domestic
product; therefore, it is prudent to take measures to contain health care costs. The
contributors to financing health care for 2011 were households at 28%, the federal
government at 28%, private business at 21%, state and local government at 17%, and
other private revenue at 7% (Centers for Medicare and Medicaid Services, 2013).
Regulating health care. Regulatory practices in health care are geared toward
access to care, quality care, and cost containment (Field, 2007). The Hill–Burton Act of
1946 allowed the construction of hospitals and expansion of hospitals to reduce the
geographical impediments that created barriers to accessing care (Field, 2007). In 1956,
CHAMPUS was established under the Dependent Medical Care Act to provide care to
service members’ families (Longest, 2006). The Comprehensive Health Planning and
Services Act of 1966 was amended in 1974, establishing national Health Systems

29
Agencies to regulate building or expansion of medical facilities at the state level. This act
mandated states to start a certificate-of-need program in which hospitals identified
medical and technological requirements in their health plans (Field, 2007). The Balanced
Budget Act of 1997 established many requirements under Medicare, such as revising the
reimbursement system, reducing payments for inpatient and outpatient services, as well
as expanding care to children for families who could not afford to purchase medical care
(Field, 2007; Longest, 2006).
The Health Maintenance Organization Act of 1973 mandated that health
maintenance organization options be included in the selection of health insurance
provided by employers (Field, 2007). Established in 1951, the Joint Commission on
Accreditation of Healthcare Organization, accredits hospitals, ensuring hospitals comply
with established quality stands (Field, 2007). In 1990, the National Committee for
Quality Assurance was created to provide oversight of quality for managed care
organizations in the private sector.
The Federal Anti-Kickback laws were implemented in 1972 to deter individuals
from receiving financial inducements for referrals or purchasing of goods and services
reimbursed under a federal health care program (Matyas & Valiant, 2006). Title 32 Code
of Federal Regulations Section 199 regulates CHAMPUS/TRICARE programs,
providing guidance on benefits, claims processing, accreditation, and fraud, among other
aspects of purchasing direct care (Matyas & Valiant, 2006; TMA, 2008a). The Federal
Appropriations Act of 1993 stipulated that CHAMPUS beneficiaries cannot be billed
115% over the CHAMPUS allowed charge (TMA, 2008c). The Balanced Budget Act of

30
1997 afforded the same balance billing protection for Medicare beneficiaries (Field,
2007). The balance billing protection law only applies in the United States.
Health Care in the Philippines
The Republic of the Philippines is a low middle-income country with a population
of 98,007,000 as of August 2013 (Population Reference Bureau, 2014). The Philippines
health system is a decentralized National Health Plan model in which the Philippine
Health Insurance Corporation (PhilHealth) administers the public sector health benefit
and collects the payments, whereas the Department of Health, Philippines oversees health
care policies (Boslaugh, 2013). Many Philippine citizens do not understand the benefits
administered by PhilHealth (Boslaugh, 2013).
Health expenditure 2011. In 2011, the Philippines’ total health expenditure was
PhP431 billion (National Statistical Coordination Board, 2013). Funded by various
sources, the amount of funding from each contributor were PhP116,433 billion from the
government, PhP39,126 billion from social insurance, PhP272,009 billion from private
sources, and PhP3,478 billion from grants (National Statistical Coordination Board,
2013). Therefore, private sources spent 63.1% on health care; the government spent 27%
on health care, social insurance contributed 9.1% to the cost of health care, and grants
contributed 0.8% to the cost of health care (National Statistical Coordination Board,
2013).
Selected Republic Acts. The Philippines health system underwent major changes
to adopt regulations to provide access to quality medical care by implementing various
Republic Acts (Republic of the Philippines Department of Health [PDH], n.d.). The

31
Hospital Licensure Act of 1965 was implemented to ensure that every hospital has a
license to operate (PDH, n.d.). The Medicare Act of 1969 was superseded by the National
Health Insurance Act of 1995, expanding access to care to citizens of the Philippines,
specifically, the impoverished (PDH, n.d.). The Pharmacy Act of 1987 governs the sale
of medicines in the Philippines (PDH, n.d.). The purpose of the 1999 Health Sector
Reform Agenda was to improve the facets of the Philippine health system at different
levels (PDH, n.d.). The Universally Accessible Cheaper and Quality Medicines Act,
implemented in 2008, keeps quality medicines at an affordable price for everyone (PDH,
n.d.).
Cost Containment
Several mechanisms have been implemented to reduce health care expenditures.
These mechanisms to contain rising costs in health care differ between the public sector
and private sector. In the public sector, under the Medicare program, the prospective
payment system (PPS) and the resource-based relative value system (RBRVS) are used to
control costs. The PPS controls rising costs for hospitals by establishing reimbursement
rates based on the patient’s diagnosis, whereas the RBRVS controls physicians’
reimbursement rates based on the level of expertise needed to treat a condition. Under the
Medicaid program, states have opted to determine the benefits provided to beneficiaries
who are eligible for the program as well as regulate reimbursement rates to providers. As
a cost containment measure, managed care was implemented to contain rising medical
costs (Mohaghegh, 2007; Rodwin, 2010; Weiner, Famadas, Waters, & Gikic, 2008;
Zwanziger, Hart, Kravitz, & Sloss, 2001).

32
Managed care organizations. Cost containment, access to care, and quality care
are concerns in the health industry (Mohaghegh, 2007). The development of managed
care was originally intended to control the rising cost of health care in the United States
(Mohaghegh, 2007; Rodwin, 2010; Weiner et al., 2008; Zwanziger et al., 2001).
However, Koop (1996) clarified that access to care was the catalyst for managed care, not
cost containment. Koop believed that physicians wanted the latitude to provide care to
their patients without concern if the patients could afford to pay for the medical services.
After the implementation of managed care, the focus was placed on medical practices and
disease management that produced better outcomes and utilization management that
eliminated medical procedures the patients did not need (Koop, 1996). In essence, cost
containment was an outcome of managed care.
The rising cost of health care, access to health services, and quality care were not
only concerns in the United States but also concerns in other countries (Weiner et al.,
2008). According to Schoen et al. (2010), the design of the insurance plan influences
access to medical care and costs in the United States and internationally. Vargas,
Vázquez, Mogollón-Pérez, and Unger (2010) also found that insurance design impacts
access to medical care. Patients were required to pay user fees, creating barriers to care,
affecting access to much-needed medical care. Other countries were evaluating ways to
contain their health care costs and provide oversight of medical services, so the concept
of managed care in the United States was exported to other countries (Rodwin, 2010;
Weiner et al., 2008). Some countries had difficulty with managed care, for example, the

33
first time the Philippines tried to implement managed care, managed care techniques
were not successful until later.
Schoen et al. (2010) conducted a computer-assisted telephone interview survey
March through June 2010 by the Commonwealth Fund to explore the differences in
healthcare access, cost, and care experiences based on income with different cost sharing
provisions in 11 countries including the United States. Schoen et al. found that providers
were reimbursed the same regardless of the beneficiary’s income in all countries except
the United States. In fact, Schoen et al. found that insured adults in the United States in
comparison to the other countries were more than likely to forgo medical care because of
cost, financial difficulty paying for medical care, problems with their insurance company,
and although insured, still have medical expenses.
Rodwin (2010) noted physicians provided a high amount of medical services
under the fee-for-service (FFS) payment system; however, capitation was implemented to
pay for each patient, which ended entrepreneurship and fee-for-payment conflicts.
Scholars believed that health care reimbursement differed based on the country; whereas
some countries use a FFS system, capitation, and a PPS (Rodwin, 2010; Weiner et al.,
2008), Kwon (2011) found that some Asian countries with universal health care use an
FFS reimbursement system effectively for reimbursing providers, and other Asian
countries that use FFS reimbursement systems should use a different reimbursement
system for effectiveness.
The government may finance the health care system as seen in New Zealand, but
in Singapore, the bulk of health care expenditure is privatized (Weiner et al., 2008).

34
Wagner et al. (2011) recommended passing public policy in which individuals could have
access to medical care without jeopardizing their quality of life. In various countries,
individuals have been forced to choose between receiving medical care and paying for
household goods, such as rent or food (Wagner et al., 2011).
Understanding the difference in managed care organizations (MCO) is important,
especially when medical care is delivered through an MCO instead of the traditional
insurance plan (Wagner & Kongstvedt, 2007). Each type of MCO has specific rules
beneficiaries must follow.
Health maintenance organizations. Beneficiaries must enroll in HMOs,
whereby they will be assigned a primary care manager who will coordinate their medical
care. HMOs could be reimbursed using a sliding scale, fixed fee schedule, or diagnosis-
related groups (Wagner & Kongstvedt, 2007). HMOs must ensure beneficiaries have
access to high-quality care. Cost containment mechanisms, such as utilization
management, case management, and disease management, are part of the services
provided in an HMO plan. There are staff model HMOs, group model HMOs, and
independent practice model HMOs with varying differences.
Preferred provider organizations. PPOs contract with providers to provide
medical services to beneficiaries. PPOs have a negotiated rate that includes a fixed fee
schedule, all-inclusive per diem rates, or diagnosis-related groups (Wagner &
Kongstvedt, 2007). The size of the PPO may be limited. Beneficiaries covered under
PPOs can use non-PPO providers, but coinsurance rates, such as copayments, will be

35
higher, as will deductibles (Wagner & Kongstvedt, 2007). As a cost containment
mechanism, utilization management programs are in place to contain cost.
Point of service. Wagner and Kongstvedt (2007) thought of the POS model as a
hybrid of the HMO and PPO models. Under the PPO model, the provider would be
reimbursed using a capitation method or performance-based method. The HMO model
would allow the beneficiary to seek care outside the HMO network, but the beneficiary
would be responsible for a higher deductible and coinsurance.
MCOs utilized cost constraint mechanisms, such as disease management, case
management, utilization management, and financial incentives, to contain costs (Granger,
Boyer, Weiss, Linton, & Williams, 2010; Mohaghegh, 2007).
Heath Care Fraud
Fraud contributes to the escalation of health costs. Sutherland (1940) described
fraud as “white-collar criminality” that is present in various businesses and different
professions. Health care is a lucrative industry making health systems around the world
appetizing to white-collar criminals. Savedoff and Hussmann (2005) estimated that $3
trillion or more is spent on health care globally, which makes the health care industry
more susceptible to fraud and abuse.
The Philippines is known for the widespread health care fraud and abuse activities
that contributed to the increased health care expenditures. In response to the fraudulent
and abusive activities, the DHA implemented fraud and cost control initiatives in the
hope of controlling health care costs and eliminating fraudulent billing practices in the
Philippines. These initiatives included the following:

36
1. Provider validation and certification: In the Philippines, the DHA identified a
significant number of claims submitted by providers who did not exist. The
DHA implemented a requirement that DHA must certify all Philippine
providers who serve TRICARE beneficiaries. The TOP contractor is
responsible for verifying that providers meet the Philippine government’s and
its licensing board’s established standards for credentialing and licensing. The
providers must also meet some of the U.S. standards. The certification process
requires on-site verification of the providers’ offices and inpatient facilities to
ensure they exist and are capable of providing the specified level of care
billed.
2. National drug coding (NDC): DHA required providers who exceeded the
$3,000 limit for pharmacy services in a year to submit pharmacy charges with
the NDC.
3. Prepayment review: As one of the most effective antifraud controls, the TOP
contractors reviewed claims before paying claims.
4. Government-directed foreign fee schedule: In November 2008, DHA
implemented the use of the purchasing power parity indexed fee schedule in
the Philippines. Using the country-specific index for the Philippines reflects
the actual medical costs for services rendered. The foreign-fee schedule
controls costs and reduces fraud and abuse.
5. Education: The identification of inappropriate behaviors for providers and
beneficiaries who submit claims results in educational letters sent to the

37
providers and beneficiaries explaining the inappropriate behaviors and the
consequences of the behavior.
6. Data mining tools: Data mining provides TRICARE with the technology to
transform complex and voluminous health care transactions into useful
information to detect fraud and abuse.
7. Payments and explanation of benefits mailed to providers versus billing
agents: In the Philippines, third-party agencies (TPA) submitted inflated
claims to TRICARE unbeknownst to the providers as the payments went
directly to the TPAs. As a result, TRICARE only allows for payments and
explanations of benefits mailed to the providers at the location identified on
the claims, not to the TPAs.
8. Supporting documentation: In November 2008, the DHA allowed providers
and beneficiaries to fax claims and supporting documentation to the TOP
claims processor.
9. TRICARE certified pharmacies: Providers filled prescription medications in
their offices and billed TRICARE for an office visit. DHA implemented
certification requirements for pharmacies in the Philippines, whereas
prescription medications from certified retail or hospital-based pharmacies
may be cost shared.
10. Proof of payment: In September 2012, DHA implemented a proof of payment
requirement for all health care received overseas and paid for by the
beneficiary (Carey, 2011; Scott, 2006; TMA, 2008a).

38
Department of Defense Health System
The DoD has the oldest, largest medical system, dating back to 1799, when
Congress enacted legislation to care for disabled seamen and, in 1884, extending the
health care entitlement to family members at no cost (Granger et al., 2010). Active-duty
family members could obtain care in the civilian sector after the Emergency Maternal and
Infant Care Program was passed in 1943 and the Dependents Medical Care Act was
passed in 1956, giving DoD the authority to enter into contracts with nonmilitary
providers (Barton, 2007; Coppola, Harrison, Kerr, & Erckenbrack, 2007; Granger et al.,
2010). Retirees and their family members could obtain medical care in the civilian sector
after the Military Medical Benefits Amendment was passed in 1966 (Granger et al.,
2010). As a result, in 1967, CHAMPUS was formed providing a mechanism for non-
active-duty beneficiaries to receive care in the civilian sector (Granger et al., 2010).
Approximately 500 military installations closed between 1988 and 2005 under the
Base Realignment and Closures Act, decreasing access to care in military treatment
facilities (MTF) for retirees and their family members as an effort to decrease rising
medical expenditures in the MTF (Coppola et al., 2007; Granger et al., 2010). The need
to purchase medical care in the civilian sector doubled health care expenditures, leaving
DoD to examine other ways to deliver medical care to this population. Medical care
expenditures were still out of control, so DoD conducted the CHAMPUS Reform
Initiative (CRI) from 1988 to 1993, to provide medical care using a managed care model
that mirrored managed care in the private sector. The CRI managed care model offered
three optional plans for beneficiaries: the CHAMPUS Prime option, which resembled a

39
health maintenance organization; CHAMPUS Standard, the original basic FFS option;
and CHAMPUS Extra, a hybrid of the private sector preferred provider option (Granger
et al., 2010; Zwanziger et al., 2001). This initiative was the beginning of the
transformation of CHAMPUS to TRICARE.
Military Health System
The MHS is responsible for providing health care to 9.7 million service members,
retirees, eligible family members, National Guard and Reserve members, and former
spouses all over the world (TMA, 2012). The MHS is a combination of direct care, care
received in MTFs, and purchased care, or care received in the civilian sector (Granger et
al., 2010; TMA, 2012).
The MHS mission is “to enhance the Department of Defense and our nation’s
security by providing health support for the full range of military operations and
sustaining the health of all those entrusted to our care” (TRICARE, 2012, para. 3). The
vision of the MHS is “a world-class health care system that supports the military mission
by fostering, protecting, sustaining, and restoring health” (para. 4).
TRICARE Health Plan Options
TRICARE Prime is DoD’s health maintenance organization–like option.
TRICARE beneficiaries must take action to utilize this option. Beneficiaries desiring to
use TRICARE Prime must enroll by completing an enrollment application and selecting a
primary care manager. Through enrollment in TRICARE Prime, beneficiaries will
receive medical care in MTFs or the private sector (TMA, 2009). Depending on the
beneficiary category, there will be no cost or reduced out-of-pocket cost (TMA, 2008c).

40
Active-duty family members enrolled in Prime are not subjected to an enrollment fee and
copayments, whereas retirees and their family members enrolled in TRICARE Prime will
be subjected to an enrollment fee and copayments (TMA, 2008c). Copayments are only
applicable when retirees and their family members receive care in the private sector
(TMA, 2008c). Beneficiaries enrolled in TRICARE Prime must follow the rules of
TRICARE Prime, for example, a beneficiary cannot self-refer to a specialist without
obtaining a referral from the assigned PCM and authorization provided by the contractor
for the region in which the beneficiary is enrolled. If beneficiaries receive care without
the proper referral and authorizations, they are encouraged to use their point of service
option. The TRICARE Prime option is not available worldwide (TMA, 2009).
TRICARE Standard is the basic FFS option in which CHAMPUS laid the
foundation for the benefits currently provided with enhancements (Granger et al., 2010;
TMA, 2009). The TRICARE Standard option allows the most freedom to select providers
but costs more money. The beneficiaries will be responsible for deductible and cost
shares based on beneficiary category (TMA, 2008c). There is no enrollment, and
generally, referrals and authorizations are not required with a few exceptions, for
example, inpatient treatment, skilled nursing care (TMA, 2008a, 2008b). Beneficiaries
must receive care from TRICARE-authorized providers for TRICARE to reimburse on
their claims. According to the balance billing law, providers cannot balance bill
TRICARE Standard beneficiaries more than 15% above the TRICARE maximum
allowable amount; the balance billing limitation is only applicable in the United States
(TMA, 2008c). TRICARE Standard is available all over the world.

41
TRICARE Extra is the preferred provider option in which TRICARE
beneficiaries use providers in the TRICARE network. Beneficiaries do not enroll in this
option; they are TRICARE Standard beneficiaries opting to see network providers on a
case-by-case basis in which they receive a 5 percent discount (TMA, 2008b, 2008c,
2009). Providers cannot balance bill the beneficiaries because they are network providers
who have signed contracts agreeing to accept what TRICARE allows in full (TMA,
2008b, 2008c). TRICARE Extra is only available in the United States (TMA, 2008b).
Evolution of the Military Health System
According to Granger et al. (2010), the DoD MHS is the oldest and largest health
care system, dating back to 1799, when Congress enacted legislation to care for disabled
seamen. In 1884, Congress extended the health care entitlement to family members at no
cost. The Emergency Maternal and Infant Care Program was passed in 1943, giving
active-duty family members the opportunity to obtain care in the civilian sector (Granger
et al., 2010). After the Dependents Medical Care Act was passed in 1956, DoD had the
authority to enter into contracts with nonmilitary providers (Granger et al., 2010). Active-
duty family members were given priority over retirees and their family members in
MTFs, resulting in a shortfall of appointments. As a result, the Military Medical Benefits
Amendment had passed in 1966, allowing retirees and their family members to obtain
medical care in the civilian sector (Granger et al., 2010).
Military Health Care Demonstration: CHAMPUS Reform Initiative
The health system for the military faced the same problems as other health care
systems throughout the United States and internationally. Thus the evolution for

42
CHAMPUS to incorporate TRICARE as an enhancement to the MHS started in 1988
with the CRI. The CRI was designed to decrease the costs of purchased care and direct
care, reduce the utilization of health care in the private sector, improve coordination of
care between the MTFs and civilian providers, and increase patient satisfaction
(Zwanziger et al., 2001). The DoD conducted the CRI 5-year Demonstration Project in
Hawaii and California (Zwanziger et al., 2001).
The sample frame consisted of randomly selected active-duty members and
retirees, stratified (Zwanziger et al., 2001). Eligible beneficiaries had the option to select
CHAMPUS Prime, the HMO-like option, the CHAMPUS option, the original FFS basic
program, or CHAMPUS Extra (Zwanziger et al., 2001). Secondary data, data from two
CHAMPUS beneficiary surveys and claims data for beneficiaries surveyed, were used to
evaluate cost, utilization, and patient satisfaction (Zwanziger et al., 2001). A multivariate
analysis was employed to evaluate overall cost, and multivariate regression models were
used to evaluate continuous (linear) and categorical (logistic) variables (Zwanziger et al.,
2001).
It was concluded that the CRI Demonstration was successful; although the cost of
health care increased, beneficiary satisfaction and access to care in the MTF also
increased (Zwanziger et al., 2001). The research could not determine if CRI impacted
quality.
Enhancements in TRICARE 1999 Through 2011
The DoD health care program provided services for approximately 8.3 million
beneficiaries in 1999 (TMA, 1999). In 1999, beneficiaries enrolled in TRICARE Prime

43
were automatically reenrolled; action was taken only if they did not want to reenroll
(TMA, 1999). Prime enrollees were no longer subjected to balance billing; thus, reducing
out-of-pocket expenses for enrollees. TRICARE beneficiaries no longer paid multiple
copayments for ancillary services. TRICARE aligned provider reimbursements with
Medicare reimbursement rates (TMA, 1999). During 1999, active-duty service members
geographically separated from units with MTFs were deemed TRICARE Prime Remote
so they could receive care in the private sector close to where they worked. In 1998, six
TRICARE Senior Prime Demonstration sites were launched to provide care for seniors
over 65 (TMA, 2000).
Enhancements in 2000
The DoD health care program provided services for approximately 8.2 million
beneficiaries in 2000 (TMA, 2000). Several demonstrations were established to provide
access to care for seniors who had served their country. The Federal Employee Health
Benefits Program, a 2-year Demonstration, January 2000 through December 2002,
TRICARE Senior Supplement, a 2-year Demonstration, April 2000 through December
2002, Pharmacy Redesign Pilot Program network retail and mail order pharmacy, but
beneficiary must have Medicare Part B (TMA, 2000). The Base Realignment and
Closures resulted in limited access to MTFs that affected retirees. Beneficiaries enrolled
in TRICARE Prime were assigned primary care managers by name. Case managers were
assigned to care for complex cases (TMA, 2000).

44
Enhancements in 2001
In 2001, the DoD health care program provided services for greater than 8 million
beneficiaries (TMA, 2001). TRICARE Prime Remote for Active Duty was extended to
the family members living with the service members stationed at geographically
separated units (TMA, 2001). The TRICARE Dental Program for family members and
the TRICARE Selected Reserve Dental Program provided enhanced benefits. TRICARE
for Life reinstated TRICARE benefits for retirees age 65 as long as they had purchased
Medicare Part B (TMA, 2001). As of 2001, active-duty family members enrolled in
Prime did not have to pay copayments (TMA, 2001). In select MTFs, active-duty service
members could receive chiropractic care. The catastrophic cap for retirees was reduced to
$3,000, the initiation of a nutritional program, Women, Infant, and Children Overseas,
was put in place, and the Pharmacy Data Transaction Service started to improve patient
safety (TMA, 2001).
Enhancements in 2007
Military medicine had to change from treating members during peacetime to
treating members during wartime. Military members are indoctrinated to fight wars, so
they must be indoctrinated back into the civilian sector once their tour of duty is over.
Military providers and civilian providers had to be equipped to treat posttraumatic stress
disorder (PTSD), traumatic brain injuries, and amputees capable of returning to work
(TMA, 2012).

45
Enhancements in 2011
Fast forwarding to 2011, the implementation of the TRICARE Young Adult
(TYA) benefit was in response to the Patient Protection and Affordable Care Act of 2010
that required private medical insurance companies to allow parents to provide medical
coverage for their children up to age 26 (TMA, 2012). TRICARE benefits typically
covered children up to age 21 or age 23 if in college full-time or older if disabled (TMA,
2009). The beneficiary has the option under TYA to enroll in TRICARE Prime or use
TRICARE Standard, but the beneficiary must pay a premium (TMA, 2012). The contract
for the TRICARE Dental Program was awarded to a different contractor resulting in
lower premiums for all beneficiaries and allowing those beneficiaries and survivors not
previously enrolled to enroll (TMA, 2012). Generic pharmacy drugs copayment reduced
to zero in October 2011 through the TRICARE Pharmacy Home Delivery. The
enhancements listed above are not all-inclusive.
Assessment of Patient Satisfaction
Evaluations must be conducted to determine if policy enhancements or
demonstrations achieved the expected outcome. One way to determine if the expected
outcome has been achieved is by conducting a satisfaction survey. Patient satisfaction is
an important dimension for measuring access, quality, and cost. Studies have been
conducted to evaluate patients’ satisfaction with the type of plan option selected, like the
survey assessing patient satisfaction with services provided by the primary care clinics
that participated in the primary community care network (PCCN) Demonstration Project
in Taiwan (Lin, Lin, & Lin, 2010).

46
This survey also evaluated patient satisfaction for patients receiving care from
non-PCCN clinics. Lin et al. (2010) found that there was no difference in patient
satisfaction among PCCN member patients and non-PCCN patients for the care quality
measures. The survey also indicated that PCCN member patients would recommend the
use of the PCCN clinics to others, unlike the nonmember patients, because of their
satisfaction with the quality of their relationship with the doctor (Lin et al., 2010). Lin et
al. also found that PCCN providers who had trusting relationships with their patients
could recruit patients to become members of the PCCN.
Lin et al. (2010) and Calnan and Rowe (2006) believed that trust relations in
health care between patients and providers were important. The survey depicted that the
responsibility for erosion of trust between patient and provider was the health care
provider. Calnan and Rowe conceded that the concept of trust correlates with patient
satisfaction.
Owusu-Frimpong et al. (2010), in their study, focused on public and private
health care users in the United Kingdom: The patients in the public health care sector
were not satisfied with the relationship or attention they received from their providers.
Friesnor, Neufelder, Raisor, and Bozman (2008) found that business processes modeled
after the concept of continuous process improvement could be implemented by health
care organizations to increase the satisfaction of patients who are already satisfied by
evaluating patient concerns other than medical, for example, assessing registration
processes and parking facilities. Owusu-Frimpong et al. (2010) used a mixed method,
qualitative (semistructured face-to-face interviews) and quantitative (cross-sectional

47
survey, 5-point Likert scale) methodology to evaluate patient satisfaction with access to
care. Owusu-Frimbong et al. employed an analysis of variance (ANOVA) to explore and
compare the respondents’ perceptions of access to care to their experience with access to
care. The Pearson chi-square statistics and associated p-values were used to establish the
extent of correlations between overall patient satisfaction and the patients’ demographics
(Owusu-Frimpong et al., 2010).
Price et al. (2014) conducted a review of the literature on “the associations
between patient experience measures and other indicators of health care quality” (p. 525)
to determine the logical connection between patient experiences and measures of
structure, process, and outcomes. In total, 422 articles were searched, but 34 articles,
from 1992 to 2013, were reviewed and used for this research. The articles reviewed
methodologies that evaluated the linkage between “patient-reported experiences and
processes and outcomes of care” as well as “articles reporting on CAHPS surveys” (Price
et al., 2014, p. 525).
The literature review found a link between positive patient care experiences and
patient adherence to treatment and influenced adherence to the treatment process for
clinical outcomes for inpatient settings. It was also determined that there is a correlation
between positive patient experiences and better hospital patient safety culture, and lower
unnecessary health care utilization (Price et al., 2014). Measuring the experience of
patients in patient-centeredness care environments is important as it increases
accountability and quality improvements based on reported patient experiences.

48
Russell, Johnson, and White (2015) conducted a case study from July 1, 2011,
through June 30, 2012, using patient satisfaction data from Portage Health in the western
Upper Peninsula of Michigan. The multifacility health care system Portage Health
comprises “a 36-bed acute care hospital, several family practices, numerous specialty
medical practices and multiple hospital-owned clinics; including a university center and
express care clinics” (Russell et al., 2015, p. 1162). Press Ganey administered a 35-
question survey using a 5-point Likert scale that evaluated five areas of quality:
1. access (a1–a7), including helpfulness, promptness, courtesy, convenience,
ease of reaching the clinic by phone, and ease of scheduling appointments
2. moving through the visit (v1–v7), including speed of registration; wait times
in waiting room, in exam room, and at clinic; information about delays; and
comfort and pleasantness of waiting room and exam room
3. nurse/assistant (n1–n2), including friendliness, courtesy, and the concern of
the nurse/assistant
4. care provider (cp1–cp10), including friendliness, courtesy, and concern of
care provider; explanations, information, instructions, and clear language;
time with patient; and patient confidence
5. personal issues (i1–i6), including cleanliness, safety, security, privacy,
sensitivity to patient needs, and pain control (Russell et al., 2014, p. 1162).
The survey was mailed to 6,824 patients after an encounter; 1, 514 patients
responded, in which 129 patients submitted surveys with 10 or more questions
unanswered, so 1,385 surveys were considered usable. Some of the remaining surveys

49
had missing data for demographics which were not corrected, and the other missing data
were corrected with average responses (Russell et al., 2014). Press Ganey used the
statistical package SAS/JMP to run the regression models for the overall measures of
patient satisfaction. “ANOVA F-tests and the coefficient of determination were used to
test the significance of the models” (Russell et al., 2014, p. 1166). The dependent and
independent variables, except the demographic variables, were measured using the 5-
point Likert scales. Four questions (independent variables) were included under the
Overall Assessment section of the survey: “overall cheerfulness of our practice (o1), how
well the staff worked together to care for you (o2), overall rating of care you received
during the visit (o3) and likelihood of you recommending our practice to others (o4)”
(Russell, Johnson, & White, 2015, p. 1164). The other overall assessments were
considered as dependent variables, except for “overall cheerfulness of our practice”
(Russell et al., 2015, p. 1164).
Russell et al. (2015) determined that variables for access, moving through the
visit, nurse/assistant, care provider, and personal issues did have an impact on overall
assessments of care quality. It was determined that gender and type of care provider did
not have an impact on overall patient satisfaction. It was noted that older patients, 55
years or older, responded to the mail surveys. The demographics of the nonrespondents
are unknown. Therefore, Russell et al. recommended using different methodologies for
surveys.
A study was conducted to assess access to care and medicines and household
economic burdens (Wagner et al., 2011). Wagner et al. stated, “Each year, an estimated

50
44 million households suffer severe financial hardship and 25 million are pushed into
poverty because they need to pay for health care” (p. 151). Individuals use their savings,
decrease the monies spent on food, and sell their assets to pay for health care, or they
may opt not to receive the needed health care (Wagner et al., 2011). This study was
conducted across 70 countries with varying degrees of income—22 low, 18 lower middle,
10 upper middle, and 20 high income—using the criteria established by the World Bank
in 2003 (Wagner et al., 2011). Better access to acute care and chronic care decreased the
possibility of catastrophic health care expenditures.
This particular study revealed that although most insurance companies covered
inpatient services and outpatient physician services, they did not cover the medications
prescribed during those episodes of care. The study also highlighted the correlation
between access and health care costs financial challenges. Assessment of patient
satisfaction will result in process improvement (Owusu-Frimpong et al., 2010), change in
public policy (Wagner et al., 2011), and other patient concerns among other
improvements (Friesner, 2009).
Alkhwaldeh et al. (2014) argued that in developing countries people were living
longer. Alkhwaldeh et al. conducted a cross-sectional study to evaluate the utilization
patterns for primary health care factors and predictors of utilization and nonutilization of
health care for older adults Jordan within the past 1,6, and 12 months. The sample frame
consisted of 190 participants age 50 and older, 79 participants in the South, 85
participants in the center, and 26 participants in the North, in the Irbid governorate of
Jordan (Alkhwaldeh et al., 2014).

51
Alkhwaldeh et al. (2014) used Andersen’s behavioral use model to assess the
predisposing, enabling, and need factors to determine the patterns associated with the
utilization of primary health care services. The dependent variables were primary health
care service utilization in the past 1, 6, and 12 months. The research question was “Did
you visit the primary health care center in your region during the past month? Past 6
months? Past 12 months?” (Alkhwaldeh et al., 2014, p. 2). The independent variables
were predisposing (age, gender, tobacco use, employment status, education level, and
marital status), enabling (monthly insurance and health insurance coverage), and need
(chronic illness self-reports; Alkhwaldeh et al., 2014). Alkhwaldeh et al. used the Elderly
Cognitive Assessment Questionnaire instrument to measure older adults’ cognitive
impairment.
A Likert scale 1 to 10, 1 represented the “worst I have ever felt,” and 10
represented the “best have ever felt,” was used to measure the perceived general health of
the participants (Alkhwaldeh et al., 2014, p. 2). The participants were asked, “What
number would best represent your general health today? 6months ago? 12months ago?”
(pp. 2–3).
Alkhwaldeh et al. (2014) also used the 12-item Short Form Health Survey version
2 to measure the perceived general health status for the past 1 month. The domains
identified were “physical function, role-physical, bodily pain, general health, vitality,
social functioning, role-emotional, and mental health” (p. 3) labeled as physical
component summary (PCS) and mental component summary (MCS).

52
The data were analyzed using descriptive statistics, chi-square test of association
for categorical variables, Pearson correlations to measure associations between
independent and dependent variables, and other correlation tests (Spearman’s rho, point
biserial 𝑟, phi coefficient (𝜙), and Cramer’s V methodology; Alkhwaldeh et al., 2014).
Alkhwaldeh et al. created binary logistic models to analyze the predictors of primary
health care service utilization in the past 1 month, past 6 months, and past 12 months.
The University of Jordan School of Nursing and the Jordan Ministry of Health
Ethical Committee granted Alkhwaldeh et al. (2014) permission to conduct this study.
Alkhwaldeh et al. informed the participants that their responses would be confidential
and their identity would remain anonymous. Alkhwaldeh et al. obtained informed verbal
consent from all those involved in the study.
The limitations disclosed were the self-reported use of health care services,
chronic illnesses, and participants’ health status, and generalization of the results for
using primary health care services in other governorates or Jordan could not be done
(Alkhwaldeh et al., 2014). Alkhwaldeh et al. had to take precaution to eliminate recall
bias.
Data were analyzed for 190 older adults in which the average age of the
participants was 64.6 (6.7 SD), and 57.4% were male and 42.6% female. Of the 190
participants, 88.4% were married, 36.8% were not formally educated, 42.1% had a
primary school education, and 21.1% had a secondary education or higher; 93.7% of
participants reported they had health insurance when 6.3% participants reported they did
not have health insurance (Alkhwaldeh et al., 2014). The income mean per month per

53
participant was 218.2 (88.7 SD) Jordanian dinar currency; 27.9% participants reported
they did not have a chronic illness, when 72.1% reported they did have a chronic illness,
and 96.8% participants reported they had no cognitive impairment, when 3.2%
participants reported they had cognitive impairment (Alkhwaldeh et al., 2014). The
perceived general health status in the past month PCS average was 41.28 (11.0 SD), and
the MCS average was 50.46 (7.3 SD; Alkhwaldeh et al., 2014). The perceived health
status in the past 6 months was 6.46 (1.3 SD) and in the previous 12 months was 6.64
(1.3 SD; Alkhwaldeh et al., 2014).
Alpha levels of 0.05* and 0.01** were used for this study. Older adults who used
significantly more primary health care services in the past 1 month (a) had no formal
education or had a primary school education, p = −0.220**, (b) were nonsmokers, p =
−0.162*, (c) had a chronic illness, p = .453**, (d) had perceptions of poorer health status
today, p = −0.272**, and (e) had symptoms or poor physical health, p = −0.377**
(Alkhwaldeh et al., 2014).
The factors significantly associated with increased primary health care services
utilization in the past 6 months were (a) increasing age, p = 0.229**, (b) being
unemployed or retired, p = 0.178*, (c) having no formal education or only a primary
school education, p = 0.200**, (d) being nonsmokers, p = −0.166**, (e) having a chronic
illness, p = .633**, (f) those having poor self-rated general health status today, p =
−0.355**, and (g) those having a poor self-rated general health status in the past 6
months, p = 0.409** (Alkhwaldeh et al., 2014).

54
The predictor variables associated with significantly greater primary health care
utilization in the past 12 months were (a) increasing age, p = 0.205**, (b) being
unemployed or retired, p = .218**, (c) having no formal education or only a primary
school education, p = −.240**, (d) being nonsmokers, p = −.145*, (e) having a chronic
illness, p = .650**, (f) those having poor self-rated general health status today, p =
−.373**, and (g) those having poor self-rated general health status in the past 12months,
p = −.306** (Alkhwaldeh et al., 2014).
Alkhwaldeh et al. (2014) concluded that although chronic illness was the most
significant predictor of primary health care services utilization, all the factors could be
linked to the use of primary health care services.
Van de Ven (2014) conducted a secondary analysis of longitudinal data from
patient experience surveys carried out in 1996 and 1997 by the Picker Institute in Boston,
Massachusetts, and data from the Healthcare Organization Survey (HOS). Van de Ven
wanted to determine the relevant attributes linking satisfaction to patient experience of
care as well as the causal connection between “dimensions of care to clinic size,
economic performance, and employee job satisfaction” (p. 131). Data collected from the
HOS in 1996 and 1997 was used to assess the attitudes of providers (Van de Ven, 2014).
The third data set collected for this study comprised data from records audited for
productivity and the second year profits for both clinics (Van de Ven, 2014). Van de Ven
examined the contextual factors (clinic size and clinic employee job satisfaction), process
factors (activities performed by healthcare providers and staff), and outcome factors

55
(overall patient satisfaction and indicators of clinic performance—physician productivity
and clinic profitability). The goals of this research were
1. to empirically identify and determine the relative importance of different
aspects of the patient care experience as they relate to overall satisfaction of
patients served by primary care clinics
2. to determine how the various dimensions of care experienced by patients
relate to patient characteristics, clinic size, and economic performance as well
as the attitudes of clinic physicians, nurses, and staff toward their work as
clinical care providers. (Van de Ven, 2014, p. 132).
The sampling frame for the patient experience survey consisted of 8,363 patients
in the first year and 7,733 patients in the second year. The patients participating in the
study received medical services from the primary care clinics that were part of a large
medical group in an integrated health system located in two states in the Midwest (Van
de Ven, 2014). The patients could receive services such as obstetrics and gynecology,
family practice, and internal medicine at the clinics (Van de Ven, 2014).
After removal of the patients’ personal identifying information, Van de Ven
(2014) evaluated 23 questions from the survey. The independent variables for the patient
survey were participative provider care, staff courtesy, health status, staff follow-up,
waiting, and medical explanations, and the dependent variable was overall satisfaction
(Van de Ven, 2014). Based on the responses of the participants, the study showed strong
correlations between participative patient care and staff courtesy (r = .41 for 1996 and
1997; Van de Ven, 2014, pp. 133, 136). The previous two variables were found to be

56
directly related to staff follow-up (r ≥ .27 in 1996 and ≥ .24 in 1997) and medical
explanations (r ≥ .29 in 1996 and ≥ .28 in 1997; Van de Ven, 2014, pp. 133, 136). The
results showed participative provider care, and staff courtesy had an indirect association
with waits and delays (r = −.33 in 1996 and −.30 to −.32 in 1997; Van de Ven, 2014, pp.
133, 136). However, correlations between patients’ self-reported health status and the
other elements were less than .08 in magnitude.
Van de Ven (2014) examined the correlation between specific patients’
demographics (gender, age, and education), patients’ “willingness to recommend the
clinic to family and friends, satisfaction with the purpose of the visit, and overall visit
rating” (pp. 133–134), and patient care experience. Van de Ven reported that patient
demographics and satisfaction measures had a direct and significant correlation with
participative provider care, staff courtesy, staff follow-up, and medical explanations. Van
de Ven reported an indirect correlation between participative provider care, staff
courtesy, staff follow-up, and medical explanations in regard to waiting time. However, it
was reported that there was not a correlation to the self-reported health status (r ≤ .08)
(Van de Ven, 2014). Van de Ven did report a finding of some exceptions to correlations
between patient age and health status (r = .24 in 1996 and .27 in 1997) and patient
education and health status (r = −.23 in 1996 and −.22 in 1997). Van de Van found that
gender and level of education did not play a role in “determining patients’ assessments of
their care experience” (p. 133); however, most of the correlations fell below .06 and were
statistically insignificant.

57
Van de Ven (2014) used factor analysis to determine the variance in patient
responses, alpha coefficients to determine internal consistency, and because of the
assumption of correlations between satisfaction elements, the principal component
analysis with oblique rotation was used. A multiple regression analysis was employed to
determine the importance of the six care experience elements based on the perspective of
the patient’s visit using a 5-point Likert scale with a range from poor to excellent (Van de
Ven, 2014).
The sampling frame for the HOS consisted of 69 managers, 153 physicians, 429
nurses and clinicians, and 318 support staff in the first year and 83 managers, 207
physicians, 524 nurses and clinicians, and 334 support staff in the second year (Van de
Ven, 2014). Van de Van employed correlations and regression analysis to evaluate the
relationship between the patient experience of care and job satisfaction (doctors, nurses,
and staff, clinic size, and performance). Van de Van averaged the patients’ responses for
clinics that provided the medical services. Van de Van also averaged responses to the
HOS of the employees who worked in those clinics. Van de Van merged the data for size,
profitability, and physician productivity for the clinics. After cleaning the data, the
analysis was performed for 42 clinics. Van de Van reported “patient satisfaction was not
highly correlated with employee job satisfaction (r = .04), patient satisfaction was
negatively correlated with clinic size (r = - .40), and patient satisfaction was not
correlated to clinic profitability (r = .04) or clinic productivity (r = .02)” (pp. 136–137).
Clinics’ increase in profits, employees’ job satisfaction, clinic size, and the productivity
of the providers at clinics did not influence patient satisfaction (Van de Ven, 2014).

58
Causes for Rising Health Care Expenditures
The United States finds rising health care expenditures challenging to control.
Bodenheimer (2005a) explained the opposing roles of each actor, which was described as
a “battleground” between the actors (purchasers and insurers) who expended dollars on
health care and the actors (providers and suppliers) who received dollars for providing
health care services. The providers and suppliers are against containing health care costs,
whereas purchasers and insurers are for containing health care costs (Bodenheimer,
2005a). Bodenheimer examined several perspectives for the reason of rising health care
costs and cost containment.
Bodenheimer (2005a) found that some scholars had a difference of opinion
regarding the emphasis placed on rising health care costs. Some scholars see rising health
care costs not as severe as some might think because of the increase in jobs for the
economy and increase in healthy outcomes (Bodenheimer, 2005a). Other scholars see
rising health care costs as a primary concern because health care becomes unaffordable
and impacts the purchasers of health care patients, local and state governments, and
employers (Bodenheimer, 2005a). Bodenheimer believed that forces outside the scope of
health care factored into the increasing health care costs. Bodenheimer argued that the
economy is a driving force for growing health care costs. When a country is wealthy, the
country pays more for health care per capita. Bodenheimer also looked at the
demographics of an aging population as a possible cause for rising health care costs.
Research has shown an increase in the elderly and the rate of growth for health care

59
spending for this population, but these increases are slow, so the impacts on rising health
care costs are minimum (Bodenheimer, 2005a; Meara, White, & Cutler, 2004).
Policy gurus thought that health care costs would continue to rise without market
competition and patients cost sharing on their medical care (Bodenheimer, 2005a). They
argued that the cost of health care would be set by supply and demand in a competitive
market versus an individual entity (Bodenheimer, 2005a). This concept assumed that
purchasers would be able to make astute decisions when purchasing health care. One
major contributor to rising health care expenditures is technologic advances
(Bodenheimer, 2005b). New technology used to treat medical conditions can improve
health outcomes where the old technology lagged. Cutler and McClellan (2001) evaluated
the benefits and costs of technologic advances. The scholars examined five conditions:
(a) breast cancer, (b) cataracts, (c) depression, (d) heart attacks, and (e) low birth weight.
The cost of the technology for treating cataracts, depression, heart attacks, and low birth
weight did not outweigh the cost of the benefits for treating these conditions (Cutler &
McClellan, 2001). However, the cost of the technology used to diagnose and treat breast
cancer and the health outcomes balanced each other.
Bodenheimer (2005b) found that administrative costs contributed to rising health
care expenditures. Public and private insurers burden providers with administrative
responsibilities such as billing for patient services. Administrative overhead is higher for
private insurers than public insurers (Bodenheimer, 2005b). Bodenheimer argued that
simplifying the insurance system would help contain cost. Scholars asserted that the
absence of strong cost control measures such as expenditure caps and global budgets

60
contribute to health care expenditures rising (Bodenheimer, 2005b). Expenditure caps and
global budgets have their drawbacks. When expenditure caps are implemented, providers
have a tendency to increase the quantity of services provided to patients. This is known as
“volume creep” (Bodenheimer, 2005b). When physicians in Canada increased the volume
of services rendered, there was a reduction in the fee for the services provided to avoid
exceeding the yearly expenditure cap (Bodenheimer, 2005b). In the United States,
Medicare implemented a sustainable growth rate mechanism that tracks providers’
expenditure targets (Bodenheimer, 2005b). With this mechanism in place, physicians
who exceed the expenditure target would have their fees for the following year reduced.
Bodenheimer argued that global budgets would be most effective under a single payer.
Administrative costs would be reduced, and some providers may be allowed to make
decisions on how the budget is spent (Bodenheimer, 2005b). A disadvantage of global
budgets is that the budget can be too small, impacting access to high-quality care by
limiting access to new technology (Bodenheimer, 2005b).
Scholars argued that when providers of care have market power, the cost of health
care increases rapidly, and when health care purchasers have market power, the cost of
health care increases slowly. Market power for the provider is when an insurer signs a
contract with the provider for the rate requested resulting in lucrative reimbursements
(Bodenheimer, 2005c). Market power for the insurer is when the insurer does not sign a
contract with the provider for the rate requested (Bodenheimer, 2005c). Bodenheimer
asserted that the market power for providers could be controlled by offsetting the power
of providers and insurers as well as implementing regulations.

61
Bodenheimer (2005c) examined the relationship between high health care
expenditures, provider fees, and increased utilization of services. Comparison of the cost
of health care in the United States to the cost of health care in other countries for similar
medical conditions and procedures reveals that they cost more in the United States than in
other countries (Bodenheimer, 2005c). Health care economists believe that the method in
which providers are reimbursed affects rising health care expenditures. Economists
argued that physicians who were reimbursed under the FFS reimbursement method
performed more services than providers who were reimbursed under the capitation
reimbursement method. Providers reimbursed under the capitation reimbursement
method share financial risk for services provided to the patients so that they would limit
the number of services (Bodenheimer, 2005b). Physicians in other countries were slow
using new technology unlike physicians in the United States (Bodenheimer, 2005b). For
example, physicians in the United States may increase the number of services such as
magnetic resonance imaging (MRI) scans; whereas, other countries would not increase
the use of MRI scans or have an MRI scanner.
Cost containment strategies can be implemented after identifying contributing
factors to increasing health care costs. As noted by Bodenheimer (2005a, 2005b, 2005c),
administrative costs, an aging population, lack of market competition, patients not cost
sharing on their medical expenses, technological advances, and the nation’s economy
contributed to growing health care costs. However, Bodenheimer (2005a) and other
scholars found that the elderly population contribution to increasing the cost of health

62
care was minute. Technologic advances were seen as a major contributor to rising health
care costs.
Critical Analysis
Critical Analysis of Theoretical Frameworks
Understanding the complexity of access to quality care is paramount but often
misunderstood by those trying to access a system that provides quality care. Andersen’s
behavioral model of health services use has undergone several modifications but is
frequently used as a framework to determine and assess the individual needs to accessing
and utilizing health care. The Andersen’s behavioral use model incorporated the
importance of national policy on access to care as well as provided various individual
determinants that may influence the access to care. Andersen’s model does not inform
decision makers if the individuals who need care received the care when care was needed
as well as where care was needed. However, Andersen’s behavioral use model is useful
for providing a point of entry to the health care system.
The point of intersection of the Andersen and Donabedian theoretical models
plays a crucial role in accessing health care and developing a health care system that
provides quality care. Donabedian argued that the availability of facilities not be an
assurance of access to care (Aday & Andersen, 1974; Donabedian, 1972, 1980). The
health care system with the appropriate number of facilities with the right mix of
providers to patient ratio is essential to “protecting and promoting the quality of care”
(Donabedian, 1980, p. 82). Therefore, as Donabedian pointed out having the facilities in

63
place does not necessarily mean that individuals are receiving quality care, they must
have access to enter into the system to receive care.
Using Andersen’s and Donabedian’s theoretical models together places emphasis
on the need for a change in policy for access to quality care and the impact of that policy
changes factor into patient experience.
Critical Analysis of Literature on Methodology
Based on the literature review, researchers have used descriptive statistics,
correlation, and regression analysis. Alkhwaldeh et al. (2014) used descriptive statistics,
chi-square test of association for categorical variables, Pearson correlations to measure
associations between independent and dependent variables, and other correlation tests
(e.g., Spearman’s rho, Point Biserial 𝑟, Phi coefficient (𝜙), and Cramer’s V methodology)
in a cross-sectional study to evaluate the utilization patterns for primary health care
factors and predictors of utilization and nonutilization of health care for older adults
Jordan. As previously mentioned, Alkhwaldeh et al. concluded that although chronic
illness was the most significant predictor of primary health care services utilization, all
the factors could be linked to the use of primary health care services.
Owusu-Frimpong et al. (2010) employed an ANOVA to explore and compare the
respondents’ perceptions of access to care to their experience with access to care. The
Pearson chi-square statistics and associated p-values were used to establish the extent of
correlations between overall patient satisfaction and the patients’ demographics (Owusu-
Frimpong et al., 2010). Owusu-Frimpong et al. found significant problems with access to
care.

64
Van de Ven (2014) analyzed the correlation between patient experience
(participative provider care, staff courtesy, health status, staff follow-up, waiting, and
medical explanations) and patient satisfaction in the first and second year. Correlations
between participative patient care, staff courtesy follow-up, and medical explanations
were strong and positively correlated to patient demographics and satisfaction elements
(Van de Ven, 2014, pp. 133, 136). Correlations between participative provider care and
staff courtesy were negatively correlated with waits and delays (Van de Ven, 2014).
Correlations for gender and education were not statistically significant (Van de Ven,
2014). Van de Ven employed a multiple regression analysis to determine the importance
of the six care experience elements based on the perspective of the patient’s visit using a
5 point Likert scale with a range from poor to excellent. The results indicated the most
powerful predictors of patient satisfaction were participative provider care and staff
courtesy (Van de Ven, 2014).
Zwanziger et al. (2001) conducted a study using secondary data; data from two
CHAMPUS beneficiary surveys and claims data for beneficiaries surveyed were used to
evaluate cost, utilization, and patient satisfaction for a 5-year CRI demonstration.
Zwanziger et al. used multivariate analysis to examine overall cost, and multivariate
regression models were used to assess continuous (linear) and categorical (logistic)
variables. Zwanziger et al. concluded that the CRI demonstration was successful:
Although the cost of health care increased, beneficiary satisfaction and access to care in
the MTF also increased.

65
The literature review found a link between positive patient care experiences and
patient adherence to treatment and influenced adherence to the treatment process for
clinical outcomes for inpatient settings. Price et al. (2014) determined that there was a
correlation between positive patient experiences, better hospital patient safety culture,
and a decrease in unnecessary health care utilization. As mentioned earlier, measuring the
experience of patients in patient-centeredness care environments is vital as it increases
accountability and quality improvements based on reported patient experiences.
The statistical tests discussed are relevant to this descriptive cross-sectional study.
The tests would provide a summary of the data, information whether to accept or reject
the hypothesis, the correlation between and within the variables, predictors for accessing
care, and relevant elements for patient experience that could increase patient satisfaction.
Summary and Transition
In summary, this chapter provided information on the theoretical frameworks,
Andersen’s behavioral use model, and Donabedian’s quality of care model, used for this
research, and explained the health care system in the United States and the Philippines.
This section also provided information regarding the MHS and the evolution of the
TRICARE benefit as well as major themes from the relevant literature regarding
managed care and the importance of measuring patient experience and the statistical
analysis for assessing quality outcomes. Integrating two health care systems from two
countries is complex and challenging. As shown, there are different laws that must be
followed when the U.S. health care system is integrated with a health care system in a
different country. To achieve buy-in from providers in a host nation country, the United

66
States must devise a strategy to incentivize host nation providers to accept its
reimbursement methodology. Implementing a closed provider network Chapter 3 will
provide information regarding the sample frame, an overview of the data plan, covariates,
independent and dependent variables, ethical considerations for human subjects, and the
statistically methodology selected to explore relationships between and within variables.
The assessment of the variables identified in Chapter 3 should help determine if the
expected outcomes were or were not met and the acceptability and efficiency of an
alternative method for delivering health care to TRICARE Standard beneficiaries who
live in the Philippines and receive care in the designated Demonstration areas.

67
Chapter 3: Research Method
Data Analysis Plan
This cross-sectional quantitative study evaluated patient experience for TRICARE
Standard beneficiaries who received medical care under the DoD TRICARE Philippine
Demonstration using secondary data provided by the DHA under the DoD. The
Philippine Demonstration tested the efficacy and acceptance of an alternative approach to
health care rendered by certified Philippines providers by establishing a closed network
of approved Demonstration providers in designated Demonstration areas selected by the
DoD. The goals of the Philippine Demonstration were to control rising health care costs,
reduce aberrant billing activity, and eliminate balance billing without jeopardizing access
to high-quality health care for beneficiaries. The TOP contractor under contract with the
DoD and their subcontractor conducted the 3-year Philippine Demonstration using a
phased approach. There are three distinct phases under the Philippine Demonstration:
1. Phase 1 of the Philippine Demonstration started on January 1, 2013, in Metro
Manila and its surrounding areas: Angeles City, Pampanga; Olongapo,
Zambales.
2. Phase 2 of the Philippine Demonstration started on December 1, 2013, in the
province of Cavite, comprising General Trias, Naic, Bacoor, Imus, and Cavite
City.
3. Phase 3 of the Philippine Demonstration began on July 1, 2014, in Iloilo City,
Iloilo.
This study concentrated its efforts on the following Demonstration locations:

68
1. Phase 1 of the Philippine Demonstration started on January 1, 2013, in Metro
Manila and its surrounding areas.
2. Phase 2 of the Philippine Demonstration started on December 1, 2013, in
Cavite City.
3. Phase 3 of the Philippine Demonstration began on July 1, 2014, in Iloilo City.
This chapter includes the data analysis plan, methodology, and ethical considerations for
the project, and a concluding summary.
Operational Definitions of Variables
Independent Variable
The respondents’ gender was identified as male or female. Respondents whose
age range was between 18 and older than 62 years were included in the survey. The
TRICARE beneficiary categories are TOP Standard, TRICARE for Life, TRICARE
Retired Reserve, TRICARE Reserve Select, and TYA. These beneficiaries could be a
military retiree, family member of a military retiree, family member of an active service
member, or reserve member. Satisfaction with health care and overall satisfaction with
the Demonstration helped to assess as well as inform which attributes are important
regarding patient experience.
The coefficient variable was the designated Demonstration area (the city) in
which the care was rendered:
1. Phase 1: Metro Manila and its surrounding areas
2. Phase 2: Cavite City, Cavite
3. Phase 3: Iloilo City, Iloilo

69
Dependent Variable
Financial burdens assess if the beneficiary’s out-of-pocket cost exceeds the annual
deductible and cost share per visit and confidence that the TRICARE program can meet
their health care needs. This variable could also be indicative that the approved
Demonstration provider is not balance billing the beneficiary. Locating an approved
Demonstration provider assesses the difficulty in finding a provider.
Population
Approximately 10,000 TRICARE Standard beneficiaries live in the Philippines;
however, based on claims data, only 4,909 beneficiaries living in the Philippines used the
TOP Standard option 2 years prior to Phase 1 of health care delivery on January 1, 2013.
The targeted population for the study consisted of TRICARE Standard beneficiaries who
lived in the Philippines and accessed health care in designated Demonstration areas. The
DoD’s selection of respondents for the study was nonbiased as the survey was a
consensus survey and all beneficiaries who met the inclusion criteria had the opportunity
to respond to the survey. The respondents did not receive compensation for their
participation. Because the Philippine Demonstration was voluntary and beneficiaries
living in other provinces in the Philippines could receive care in designated
Demonstration areas, it was difficult to estimate the number of TRICARE beneficiaries
who would make up the accessible population of the study.
Sampling Frame Inclusions and Exclusions
The sampling frame included TRICARE Standard beneficiaries comprising
military retirees, family members of military retirees, and family members of active-duty

70
service members who lived in the Philippines and accessed health care in designated
Demonstration areas: Metro Manila and its surrounding areas; Cavite City, Cavite; and
Iloilo City, Iloilo. TRICARE beneficiaries enrolled in TOP Prime and TOP Prime
Remote, TRICARE Standard beneficiaries under 18 years of age unless they were
considered a TRICARE beneficiary in their own right, and TRICARE Standard
beneficiaries whose home address was not in the Philippines were excluded from
participating in the survey. The home address was determined by the address listed on the
TRICARE DoD/CHAMPUS Claim Form–Patient’s Request for Medical Payment (DD
Form 2642). The web-based survey was administered to TRICARE beneficiaries using
the e-mail addresses in M2, the information system owned by the DoD.
Sample Size
The sample size requirement was calculated for logistic regression using a
Pearson correlation with a modified power using G*Power 3.1.7. This correlation
assumed a medium effect size and a modified power of (0.80/0.91) 0.88. If statistical
significance was assessed within a 95% confidence interval (α = .050), the sample size
required to assure empirical validity was 102 (Faul, Erdfelder, Buchner, & Lang, 2013).
Accessing Data
The DHA Data Sharing Agreement Application was submitted to the DHA
Privacy and Civil Liberties Office for approval to access the government data files from
the program office that owns the data. Following the approval process, the DHA Decision
Support Division provided deidentified data on an encrypted computer disk. Obtaining
deidentified data for this research presented a problem, as the original plan was to include

71
various predisposing and enabling factors that would increase the understanding drivers
for access to health care. The data were collapsed to remove all 18 Health Information
Portability Accountability Act identifiers. I had to work closely with the analysts
providing data to obtain usable data to complete this research.
Level of Measurement
The demographic variables of interest were gender, age, and Demonstration Phase
I, II, and III. The predictor variables were (a) locating an approved provider, (b)
satisfaction with requesting a waiver, (c) financial burden and confidence that TRICARE
meets health care needs, and (d) satisfaction with health care and overall satisfaction with
Demonstration.
Methodology
This cross-sectional quantitative descriptive study included some nonparametric
analysis of relationships between specific variables. I calculated frequencies and
percentages for any categorical variables of interest, such as gender. Means and standard
deviations were calculated for any continuous variables of interest, such as age (Howell,
2010).
Data were analyzed for statistical significance using analysis of variance
calculated in SPSS Version 22. Prior to analysis, data were screened for validity, missing
data, patterns of missing data, and outliers. I used ANOVA to assure that the data met the
assumptions of independence, normality, and homogeneity variances. The Wilks–Shapiro
statistic was used to assess the assumption of normality. The Levene’s homogeneity-of-
variance test was used to assess the assumption homogeneity variance. Multicollinearity

72
was assessed by testing tolerance and the variance inflator factor within SPSS. Due to the
nonparametric nature of the Spearman rho correlation, none of the restrictive assumptions
typically associated with a correlation test needed to be met (Morgan, Leech, Gloekner,
& Barrett, 2007). I created standardized values for each scale level research variable and
examined for values that fell above 3.29 and those that fell below −3.29, which identified
outliers (Tabachnick & Fidell, 2012). Cases with missing data were also examined for
nonrandom patterns. The DHA conducted a survey evaluating the Philippine
Demonstration from which secondary data were obtained to answer the RQs for this
study. Surveys for participants who did not provide the phase in which they received care
were excluded.
Research Question 1
RQ1: How has the Demonstration affected the beneficiaries’ financial burdens
and confidence that their health care needs will be met?
H01a: There is no statistically significant relationship between financial
burdens and satisfaction with the Demonstration overall.
Ha1a: There is a statistically significant relationship between financial burdens
and satisfaction with the Demonstration overall.
H01b: There is no statistically significant relationship between financial
burdens and confidence that health care needs will be met.
Ha1b: There is a statistically significant relationship between financial burdens
and confidence that health care needs will be met.

73
To assess RQ1, I conducted two Spearman rho correlations. The first Spearman
correlation assessed the relationship between the dependent variable of financial burden
(i.e., Item 11) and the independent variable of overall satisfaction (i.e., Item 13). Item 11
asked participants to compare their out-of-pocket expenses for health care before the
Demonstration with the same expenses after the Demonstration and ranged in responses
from (a) higher now to (c) lower now. Item 13 asked about their overall satisfaction with
the Demonstration and ranged from (a) very satisfied to (e) very dissatisfied. The second
Spearman correlation assessed the relationship between the dependent variable of
confidence that health care needs were met (i.e., Item 12) and the independent variable of
overall satisfaction (Item 13). Item 12 asked participants whether the Demonstration
increased their confidence that TRICARE was able to meet their health care needs and
ranged in responses from (a) strongly agree to (e) strongly disagree. Each survey item in
the set of analyses represented an ordinal response variable. The Spearman rho
correlation was the appropriate analysis when the goal of the research was to assess the
strength or existence of a statistically significant relationship between two ordinal
variables. I used Cohen’s d (Cohen, 1988) to evaluate the correlation coefficient to
ascertain the magnitude of the difference.
Research Question 2
RQ2: What is the relationship between gender, age, and health care finder
functionality for accessing quality health care under the Demonstration in Metro
Manila and its surrounding area, Cavite City, Cavite, and Iloilo City, Iloilo?

74
H02a: There is no statistically significant relationship between gender, age,
and health care finder functionality access to quality health care in Metro
Manila and its surrounding areas, Cavite City, Cavite, and Iloilo City, Iloilo.
Ha2a: There is a statistically significant relationship between gender, age, and
health care finder functionality access to health care in Metro Manila and its
surrounding areas, Cavite City, Cavite, and Iloilo City, Iloilo.
To examine RQ2, I conducted a series of regressions. Because the relationships
between the predictors, gender and age, and the dependent variable, health care finder
functionality, were in question, I conducted a regression analyses in two stages on the
overall data set to include Metro Manila and its surrounding area, Cavite City, Cavite,
and Iloilo City, Iloilo. In the first stage, I conducted the regression on the overall data set,
and this regression included data from Metro Manila and its surrounding area, Cavite
City, Cavite, and Iloilo City, Iloilo. In the second stage of analysis for RQ2, I conducted
regressions for Metro Manila and its surrounding area, Cavite City, Cavite, and Iloilo
City, Iloilo. Findings from both the descriptive statistics and from the normality testing
for each of these regressions indicated the possibility of acquiescence bias and resulted in
a series of secondary analyses through binary logistic regression to confirm the findings.
To accomplish this, the satisfaction variable was transformed into a dichotomous
outcome, where zero represented any category less than very satisfied, and one
represented a response of very satisfied.
To examine RQ3, I conducted descriptive statistics on responses to Items 3 and 4,
as applicable. Item 3 asked participants whether they had submitted a waiver to receive

75
care from a nonapproved Demonstration provider. If participants responded that they had
submitted a waiver, the participant was asked to respond to Item 4, which asked how
satisfied they were with the provider and had response categories ranging from (a) very
satisfied to (e) very dissatisfied. Thus, responses to Item 3 were presented to show the
number who did not submit a waiver, while Item 4 identified how satisfied the proportion
of participants who did submit a waiver were with their nonapproved provider. I
conducted means and standard deviations to detail the spread and central tendency of
responses, while frequencies and percentages provided the proportionality of response
rates.
Research Question 3
RQ3: What is the relationship between a closed network, actual beneficiary out-
of-pocket cost and quality health care in Demonstration areas?
H03a: There is no statistically significant relationship between actual
beneficiary cost and a closed provider network.
Ho3a: There is a statistically significant relationship between actual
beneficiary out-of-pocket cost and a closed provider network.
H03b: There is no statistically significant relationship between quality health
care and a closed provider network.
Ha3b: There is a statistically significant relationship between quality health
care and a closed provider network.
To examine RQ3, three questions from the survey were chosen as representations
of the beneficiary out-of-pocket costs and quality health care. The first question asked

76
participants to rate their out-of-pocket costs in relation to those same costs prior to the
Demonstration. To examine the quality of health care, participants were asked to rate
their satisfaction on a scale from 0 to 10. Finally, participants were asked to compare
their current experience with receiving health care to their experience before the
Demonstration. However, to test whether these responses were significantly higher or
lower than their mid-level response categories, a series of one-sample t-tests was
conducted.
Threats to Validity
Threats to validity and reliability should be considered when designing research.
Trustworthiness and credibility come to mind when gathering data for a study. All
researchers should want to ensure that their research is reliable and valid. Bowling (2010)
asserted that a research instrument must be assessed using test–retest, interrater
reliability, and internal consistency to determine reliability. The research instrument
should be adequately tested for validity numerous times using the same population it was
intended to test before being considered valid (Bowling, 2010). A research instrument
can be reliable without being valid, but a research instrument that is not reliable is not
valid. Researchers using the same research instrument should be able to replicate the
results of previous research using the same criteria and environment (Creswell, 2009;
Field, 2007). When the research instrument measures what it is designed to measure, the
research instrument is considered to be valid (Creswell, 2009; Field, 2007). The survey
instrument that was used for this descriptive cross-sectional quantitative study was
developed, and secondary data were analyzed; therefore the instrument must be assessed

77
for reliability and validity. Creswell (2009) recommended evaluating the instrument by
determining if there is a connection between the variables, RQs, and items on the survey
instrument. Cleaning the data increased reliability, help with consistency, and accuracy.
The data cleaning process should be performed with care when removing outliers and
duplicate data. Prior to cleaning the data, a copy of the original should be saved and
security measures should be taken to protect the data. The performance of a statistical test
could determine internal consistency: Perform a reliability analysis, and check the
statistical assumptions for violations.
Statistical Conclusion Validity
Violation of a statistical assumption poses a threat to statistical conclusion
validity (Creswell, 2009). Check statistical assumptions to avoid making the wrong
conclusions. The statistical assumptions are assumptions of independence, normality,
homogeneity of variances, interval, and multicollinearity (Field, 2007). According to
Miles and Shevlin (2001), a violation of the assumption of independence can be difficult
to detect. However, when autocorrelation occurs, the assumption of independence has
been violated, which can happen with a time series design or clustered sampling design
(Miles & Shevlin, 2001). The Wilks–Shapiro statistic can evaluate the assumption of
normality. The Levene’s homogeneity-of-variance test can assess the assumption
homogeneity variance. When the distance between intervals is not equal, there is a
violation of the assumption of interval. Multicollinearity can be assessed with the
tolerance statistic and the variance inflator factor. The appropriate actions should be

78
taken to mitigate the threat of conclusion validity when there is a violation of any
statistical assumption.
Ethical Consideration
The study was submitted to the Walden University Institutional Review Board
(IRB) for approval before requesting data files and data analysis. After receiving
conditional approval from Walden University IRB, a copy of Walden University’s IRB
conditional approval was submitted to the DHA Human Research Protection Board,
which determined that human subjects would not be used for this research. After
receiving the determination from the DHA Human Research Protection Board, a Data
Sharing Agreement Application was submitted to the DHA. Upon receipt of the approved
Data Sharing Agreement Application 17–1810, the final package was submitted to
Walden University IRB for final approval. After receiving Notification of Approval to
Conduct Research from Walden University IRB (approval no.01-31-18-0082516), the
request was submitted to the Decision Support Division for access to the TRICARE
Philippine Demonstration raw survey and claims data files. Although this study consisted
of a secondary analysis, the policies and regulations for Human Research for the
Protection of Human Subjects were followed. All data have been maintained on an
encrypted removable storage disc under lock and key accessible only by the primary
investigator. After analysis, the data were stored on an encrypted removable storage disc
under lock and key accessible only to the primary investigator and will be properly
destroyed after 5 years.

79
The principal investigator (PI) for the Philippine Demonstration Beneficiary
Satisfaction Questionnaire who conducted the original research used a combination of
Web and telephone surveys and provided documentation of approval to conduct the
research from Liberty’s IRB. The PI did not target any members from vulnerable
populations. The survey participants did not receive financial incentives or gifts for their
participation. The survey was conducted over the telephone, by which the interviewers
obtained informed consent from the participants. The interviewers informed the
participants that participation in the survey was voluntary. If the participant did not want
to participate in the survey, the interviewer informed the participant that his or her
TRICARE benefits would not be affected. Additionally, the participant had the option to
stop the survey if he or she became uncomfortable. The participants were given a
telephone number to contact the PI if they had any questions as well as a different
telephone number for technical difficulties for the Web survey. The investigator did not
have any conflicts of interest.
Summary
This chapter discussed the methodology, data analysis plan, and ethical
considerations used in this cross-sectional quantitative analysis for evaluating TRICARE
beneficiaries’ satisfaction under the Philippine Demonstration. Assessing statistical
significance within a 95% confidence interval (α = .050), the sample size for the study
with a medium effect size required to assure empirical validity was 102. The database
contained approximately 8,000 TRICARE Standard beneficiaries living in the
Philippines, of whom 4,909 beneficiaries had accessed their TRICARE benefits. Chapter

80
4 presents the results of the descriptive and inferential analysis for the RQs and
hypotheses presented.

81
Chapter 4: Results
Introduction
In response to TMA’s (2008a) identification of a major concern in the Philippines
with rising health care costs, as well as the Philippines’ reputation of ubiquitous health
care fraud with TRICARE, the DHA, DoD, implemented administrative controls to deter
fraud in the Philippines (TMA, 2008a). Although the administrative controls were
implemented, the cost of health care continued to rise. Therefore, the DHA implemented
the DoD TRICARE Philippine Demonstration in 2013 to determine the efficacy and
acceptability of using an alternative method to deliver health care, increase access to
health care, and decrease beneficiary out-of-pocket costs while maintaining quality health
care. The purpose of this quantitative cross-sectional study was to address questions
regarding TOP Standard beneficiaries’ ability to access quality health care and their out-
of-pocket costs for health care under the Philippine Demonstration.
The following chapter includes a description of the data collection procedures
pertinent to the sample used for analysis. In this section are a description of the sample
and a comparison to the population of interest, intended to clarify the generalizability of
the results. The results of the analyses for RQ1, RQ2, and RQ3 follow, with an
explanation of the assumptions required for each assessment, as well as the probability
levels of the findings and an explanation of what they signify. The chapter closes with a
summary of the findings and description of what will be included in the following
discussion chapter.

82
Data Cleaning
I removed the responses such as “suppressed,” “don’t know,” and “unsure” unless
ordered correctly. For example, an unsure between agree and disagree is applicable,
while a separate category outside of Likert ranking is not. I reversed items for better
interpretability (appended with “_Reverse”):
• Q1 was recoded for higher scores indicative of higher satisfaction.
• Q4 was recoded for higher scores indicative of higher satisfaction.
• Q10 was recoded for higher scores indicative of better experience.
• Q13 was recoded for higher scores indicative of higher confidence.
Data Collection
Results
The final sample for analysis consisted of responses from 180 individuals in the
Philippines who received care under the TRICARE Demonstration and completed a
survey on their experiences with the Demonstration and health care thereafter. Of these
respondents, a majority were male (53.3%), though an additional 11.1% did not provide
this information. Exactly half of the available sample was retired, though 11.1% of the
sample provided no information regarding their beneficiary group either. Finally, though
the same 11.1% did not indicate an age, the sample consisted of a slight majority of those
within the 60–79 years of age group. Many of the sample’s participants were also within
the 40–59-year age group (n = 30, 16.7%) or 80 years or older age group (n = 28, 15.6%).
With a minority of the sample below the age of 20 (6.1%), this sample was highly

83
representative of older individuals. Demographic information for each possible grouping
of these three categories of descriptive information is available in Table 1.
Table 1
Demographic Information for Final Sample
Variable
n
%
Gender
Female
64
35.6
Male
96
53.3
No response
20
11.1
Beneficiary group
Retired
90
50.0
Retired dependent
70
38.9
No response
20
11.1
Age (years)
0–19
11
6.1
20–39
0
0.0
40–59
30
16.7
60–79
91
50.6
80+
28
15.6
No response
20
11.1
Note. N = 180.
Research Question 1
RQ1: How has the Demonstration affected the beneficiaries’ financial burdens
and confidence that their health care needs will be met?

84
H01a: There is no statistically significant relationship between financial
burdens and satisfaction with the Demonstration overall.
Ha1a: There is a statistically significant relationship between financial burdens
and satisfaction with the Demonstration overall.
H01b: There is no statistically significant relationship between financial
burdens and confidence that health care needs will be met.
Ha1b: There is a statistically significant relationship between financial burdens
and confidence that health care needs will be met.
To assess RQ1, two correlations were necessary. These two correlations follow
the associated hypotheses, focusing on the relationship between financial burden and
satisfaction and financial burden and confidence. To test a Pearson correlation with
confidence in their statistical validity, the assumption of linearity requires assessment
(Pallant, 2007). However, due to the nonparametric nature of the Spearman correlation,
this is not a requirement. The Spearman correlation was chosen as appropriate due to the
ordinal response categories for both variables in either pair in this analysis. In addition,
the use of Spearman correlations would circumvent any validiy concerns based on the
distribution of the responses concerning satisfaction or confidence, which appeard to be
skewed toward a more positive response (Lehmann, 2006). This is based on the ranking
used in Spearman correlations, which takes place in the first stage of analysis and
removes any distributional properties of the data by replacing raw values with ranks, as
needed for use in this form of correlation. For this reason, there were no assumptions that
required assessment, and the analyses could be considered valid regardless of the

85
distribution of the variables used (Lehmann, 2006). The results of both correlations were
significant and positive (satisfaction, r = .41, p < .001; confidence, r = .44, p < .001),
which indicated that, among those with higher financial burdens, their satisfaction with
the Demonstration overall and confidence that their health care needs would be met were
both correspondingly higher. Both of these correlations were statistically significant,
indicating a great degree of confidence that these correlations were accurate depictions of
reality. These findings suggest that those with a higher level of financial burden are not
only happier with the Demonstration but left feeling more confident.
Research Question 2
RQ2: What is the relationship between gender, age, and health care finder
functionality for accessing quality health care under the Demonstration in Metro
Manila, Cavite City, Cavite, and Iloilo City, Iloilo?
H02a: There is no statistically significant relationship between gender, age,
and health care finder functionality access to quality health care in Metro
Manila, Cavite City, Cavite, and Iloilo City, Iloilo.
Ha2a: There is a statistically significant relationship between gender, age, and
health care finder functionality access to health care in Metro Manila, Cavite
City, Cavite, and Iloilo City, Iloilo.
In response to RQ2, I conducted a series of regressions. Because the relationships
between the predictors, gender and age, and the dependent variable, health care finder
functionality, were in question for each region of the Demonstration, I conducted
regression analyses in two stages. In the first stage, I conducted the regression on the

86
overall data set, and this regression included data from all three locations. By assessing
these relationships, I could determine whether there was evidence of a predictive effect of
gender or age on health care finder functionality regardless of location.
Prior to analysis, I considered the assumptions of the regression. The first
assumption was the absence of multicollinearity. Though not expected due to the nature
of the independent variables, I assessed the variance inflation factor between gender and
age for any interference in the interpretation of results. A variance inflation factor above
5 is cause for concern and might indicate that the independent variables are too highly
related (Tabachnick & Fidell, 2012). This could possibly be the case if too many of one
gender were clustered within a specific age group, but it was found not to be problematic,
as the variance inflation factor’s value was 1.04. The next assumption was normality,
which concerns the normality of the distribution of error in the regression. Though the
univariate distribution of satisfaction responses regarding healthcare finder functionality
was skewed toward a more positive perception, it was important to understand the
residual normality as well, as univariate normality is not a direct assumption of the
regression analysis (Tabachnick & Fidell). This assumption is typically assessed with a
normal P-P plot, which should ideally display data points close to a hypothetically
perfect diagonal line (Tabachnick & Fidell). As seen in Figure 1, the data points did not
follow the ideal line but were not so deviant as to cause concern. However, the
assumption test’s results indicated that this analysis should still be interpreted with some
caution, as the slight deviation may cause the model estimates to be less valid. This
deviation may also have been due to the skewed distribution of satisfaction with
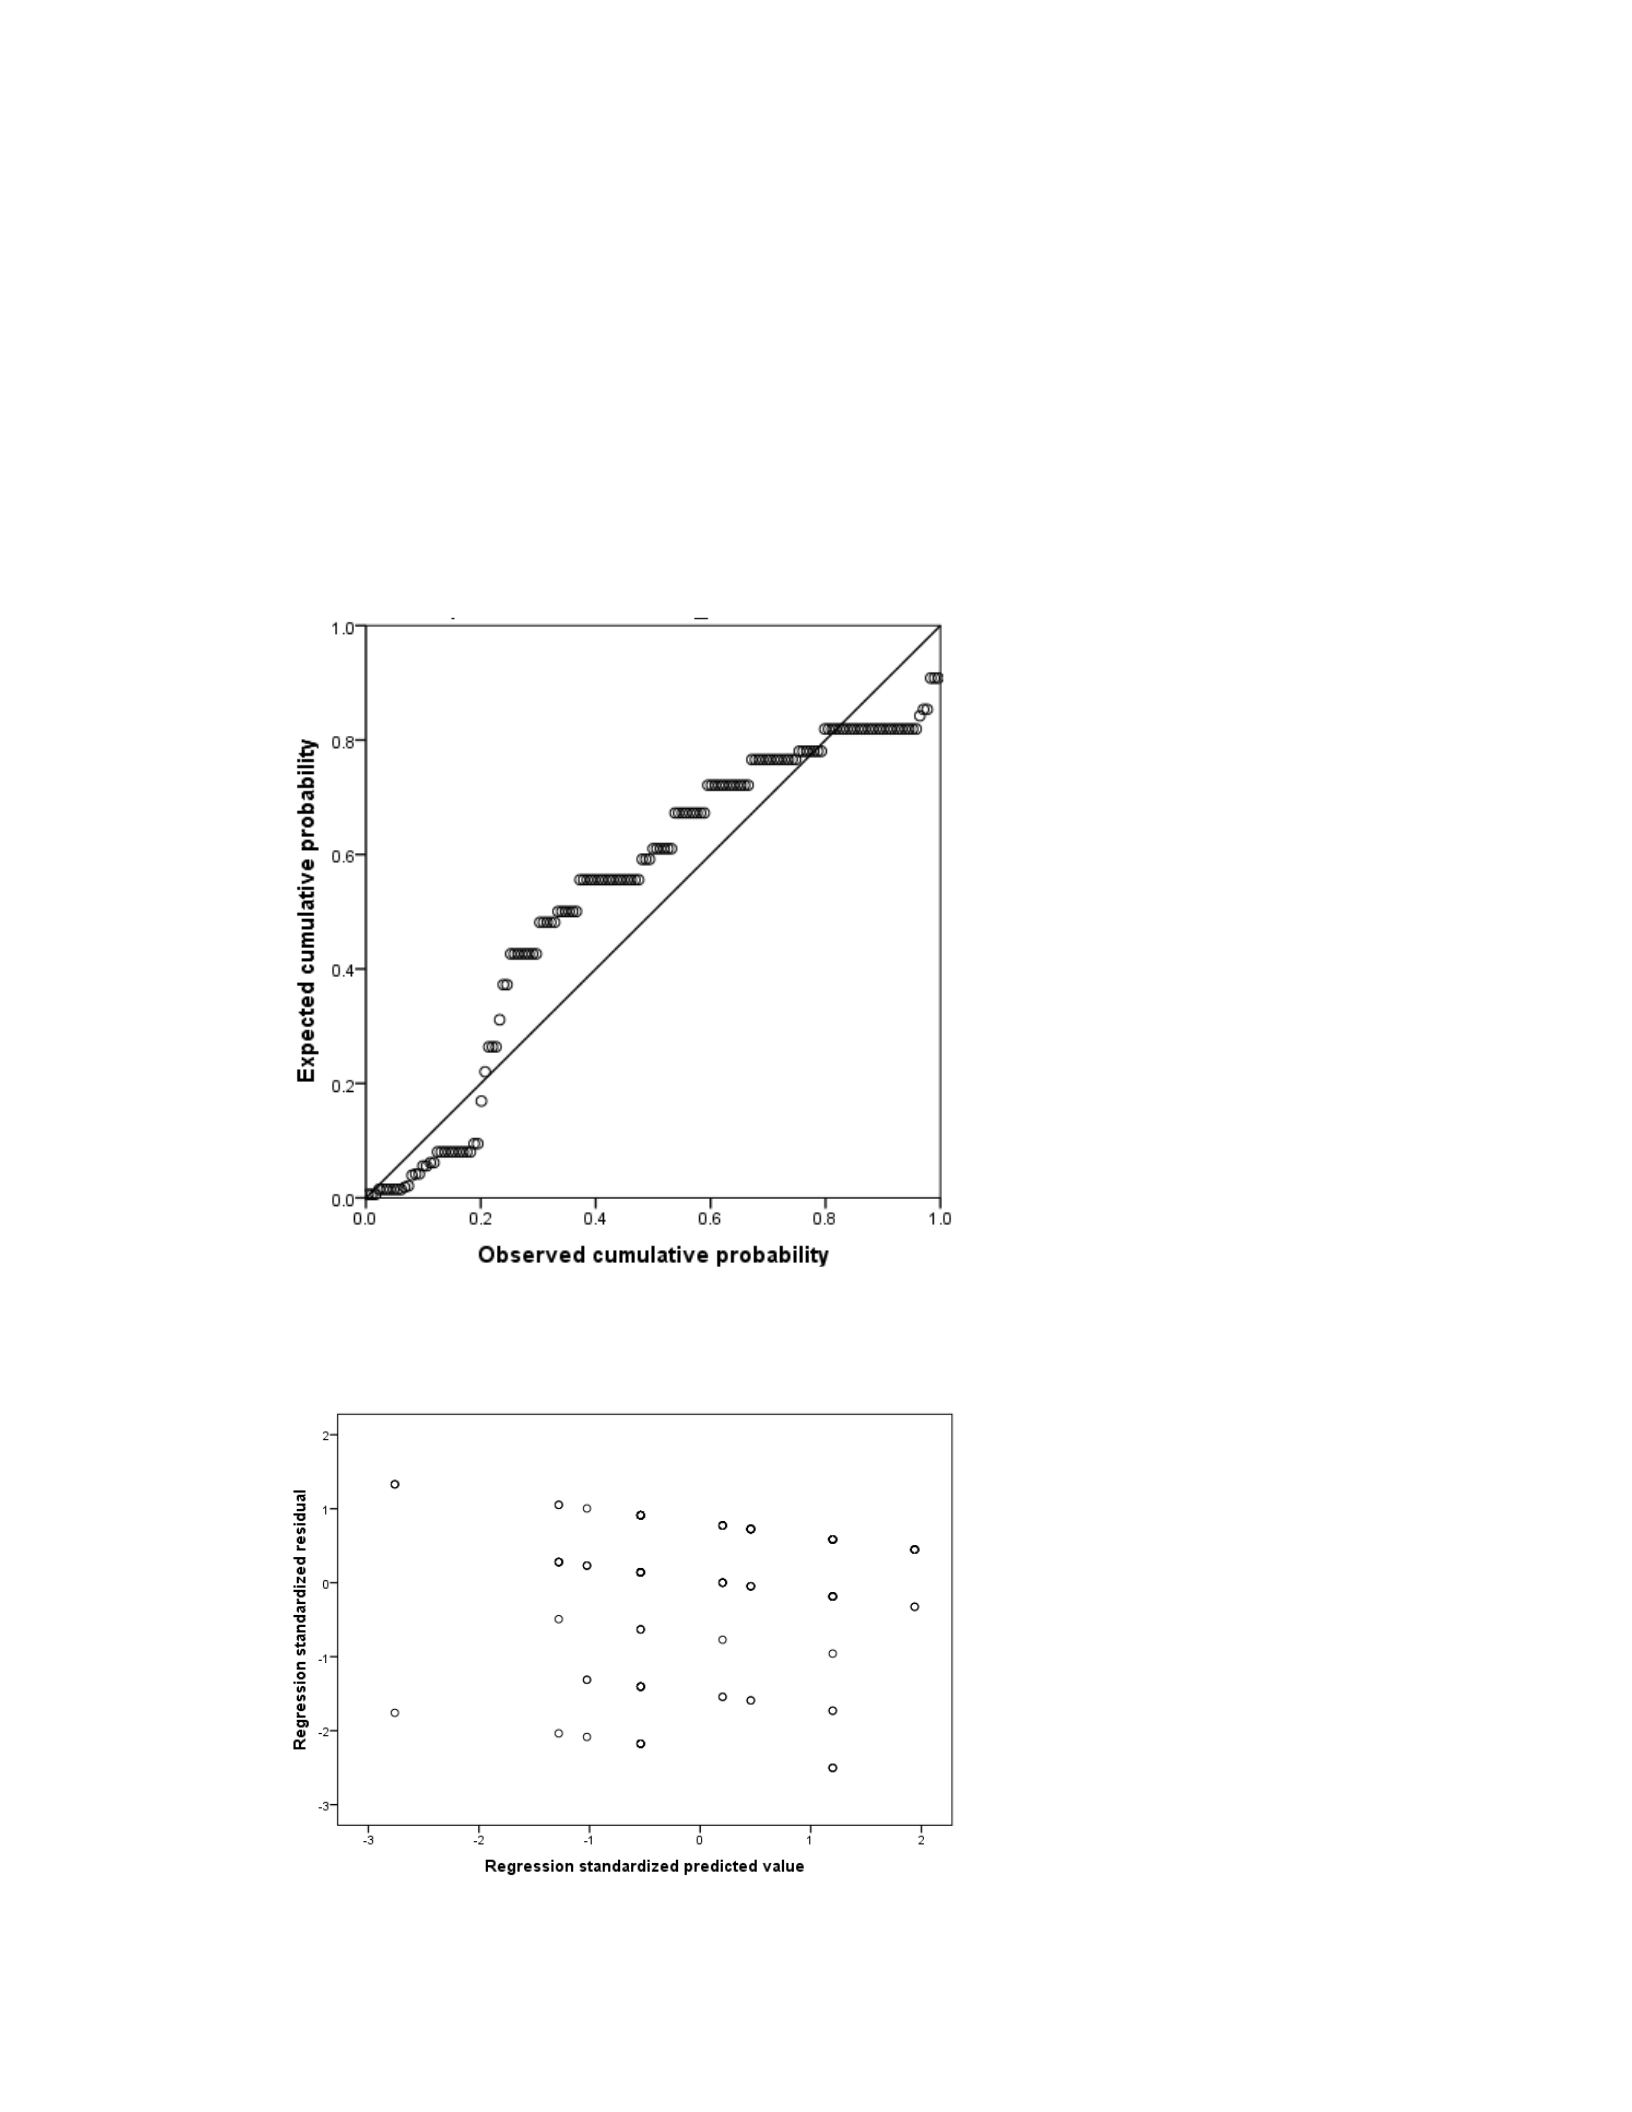
87
healthcare finder functionality. The final assumption is homoscedasticity, which is
testable through a standardized residual scatterplot (Stevens, 2016). This plot should not
show any notable pattern and is cause for concern when there is apparent funneling. As
seen in Figure 2, none such patterning was identified, and the assumption of
homoscedasticity was met.
Figure 1. Normal P-P plot for overall regression of care finder functionality.

88
Figure 2. Standardized residual plot for overall regression of care finder functionality.

89
As the results of assumption testing were questionable, the regression could be
conducted with little cause for concern as long as the results could be replicated with an
adjusted dependent variable value. To this end, satisfaction with care finder functionality,
which was skewed toward a higher satisfaction, was transformed into a dichotomous
variable for use in secondary testing. However, the originally proposed regression
analysis was conducted first. Results of the originally proposed linear regression
indicated a nonsignificant model, F(2,154) = 2.76, p = .067, R2 = .04, and did not provide
evidence that gender or age was significantly predictive of a Demonstration recipient’s
perception of health care finder functionality. This was confirmed with the findings seen
in Table 2, which show that neither predictor was significant, though gender did approach
significance. However, as predictors should not be evaluated in a nonsignificant model,
these results are not meaningful.
Following the originally proposed model, based on the understanding that the
skew in care finder functionality could have been due to acquiescence bias, the
satisfaction scale for care finder functionality was transformed into a binary variable
where zero represented any response less than very satisfied, and one represented a
response of very satisfied. This method of analysis returned similar results, with no
evidence for significance between the predictors of gender and age and the dependent
variable of satisfaction with care funder functionality (χ2(2) = 5.12, p = .077). These
findings confirmed the results of the linear regression, and thus none of the predictor
variables required interpretation.
90
Table 2
Overall Regression of Care Finder Functionality on Gender and Age
Source
B
SE
β
t
p
Gender (ref: female)
−0.42
0.22
−0.16
−1.97
0.051
Age
0.18
0.11
0.13
1.66
0.100
In the second stage of analysis for RQ2, I conducted regressions for each region
of the Demonstration individually. As a preliminary data assessment, the sample was
assessed for subsample sizes in each region. Table 3 shows these subsample sizes and
indicates that the Metro Manila subsample was much larger than both the Cavite City and
Iloilo City subsamples. Though these subsample sizes were not all-sufficient for the
regression analyses, they were conducted for completeness and based on the possibility
that effect sizes of predictive relationships within a subsample were so strong that they
lowered the required effect size to achieve significance.
Table 3
Phases of Philippine Demonstration Represented in the Data Set
Phase
n
%
Phase 1: Metro Manila
109
60.6
Phase 2: Cavite City, Cavite
39
21.7
Phase 3: Iloilo City, Iloilo
12
6.7
No data
20
11.1

91
As with the preliminary regression, assumptions were assessed for each individual
model for the three regions. Variance inflation factors for each regression were
acceptable, with a value of 1.03 for the regression conducted on Phase 1, 1.11 for Phase
2, and 1.15 for Phase 3; these values indicated that multicollinearity was not problematic
for any subsample. Normal P-P plots, seen in Figures 3, 4, and 5, were similar to the first
regression’s assumption plot within the Metro Manila regression but deviated more from
the ideal normal distribution within the Cavite City and Iloilo City subsamples. These are
likely artifacts of the small sample sizes (Cohen, 1988) and cannot be adequately
corrected with transformations or nonparametric analyses, which would require much
larger sample sizes to detect significance. In contrast to these findings, homoscedasticity
was not problematic, as the standardized residual scatterplots within Figures 3 and 4 were
satisfactory. However, homoscedasticity could not be assumed for the subsample of Iloilo
City, though this was again a likely result of the small sample size. Though these
limitations should be noted, the regression analyses were continued for completeness and
to explore any possible patterns within the data. However, in addition to these analyses, a
second series of binary logistic regressions were conducted in an effort to better
understand the results and determine whether they could be confirmed or denied through
subsequent testing. This testing took place similarly to the regression of satisfaction with
care finder functionality, with the use of a dependent variable transformed such that zero
represented any response less than very satisfied, and one represented a response of very
satisfied. The binary nature of this variable both addressed the possibility of acquiescence
bias and the non-normal distribution of residuals for each analysis.
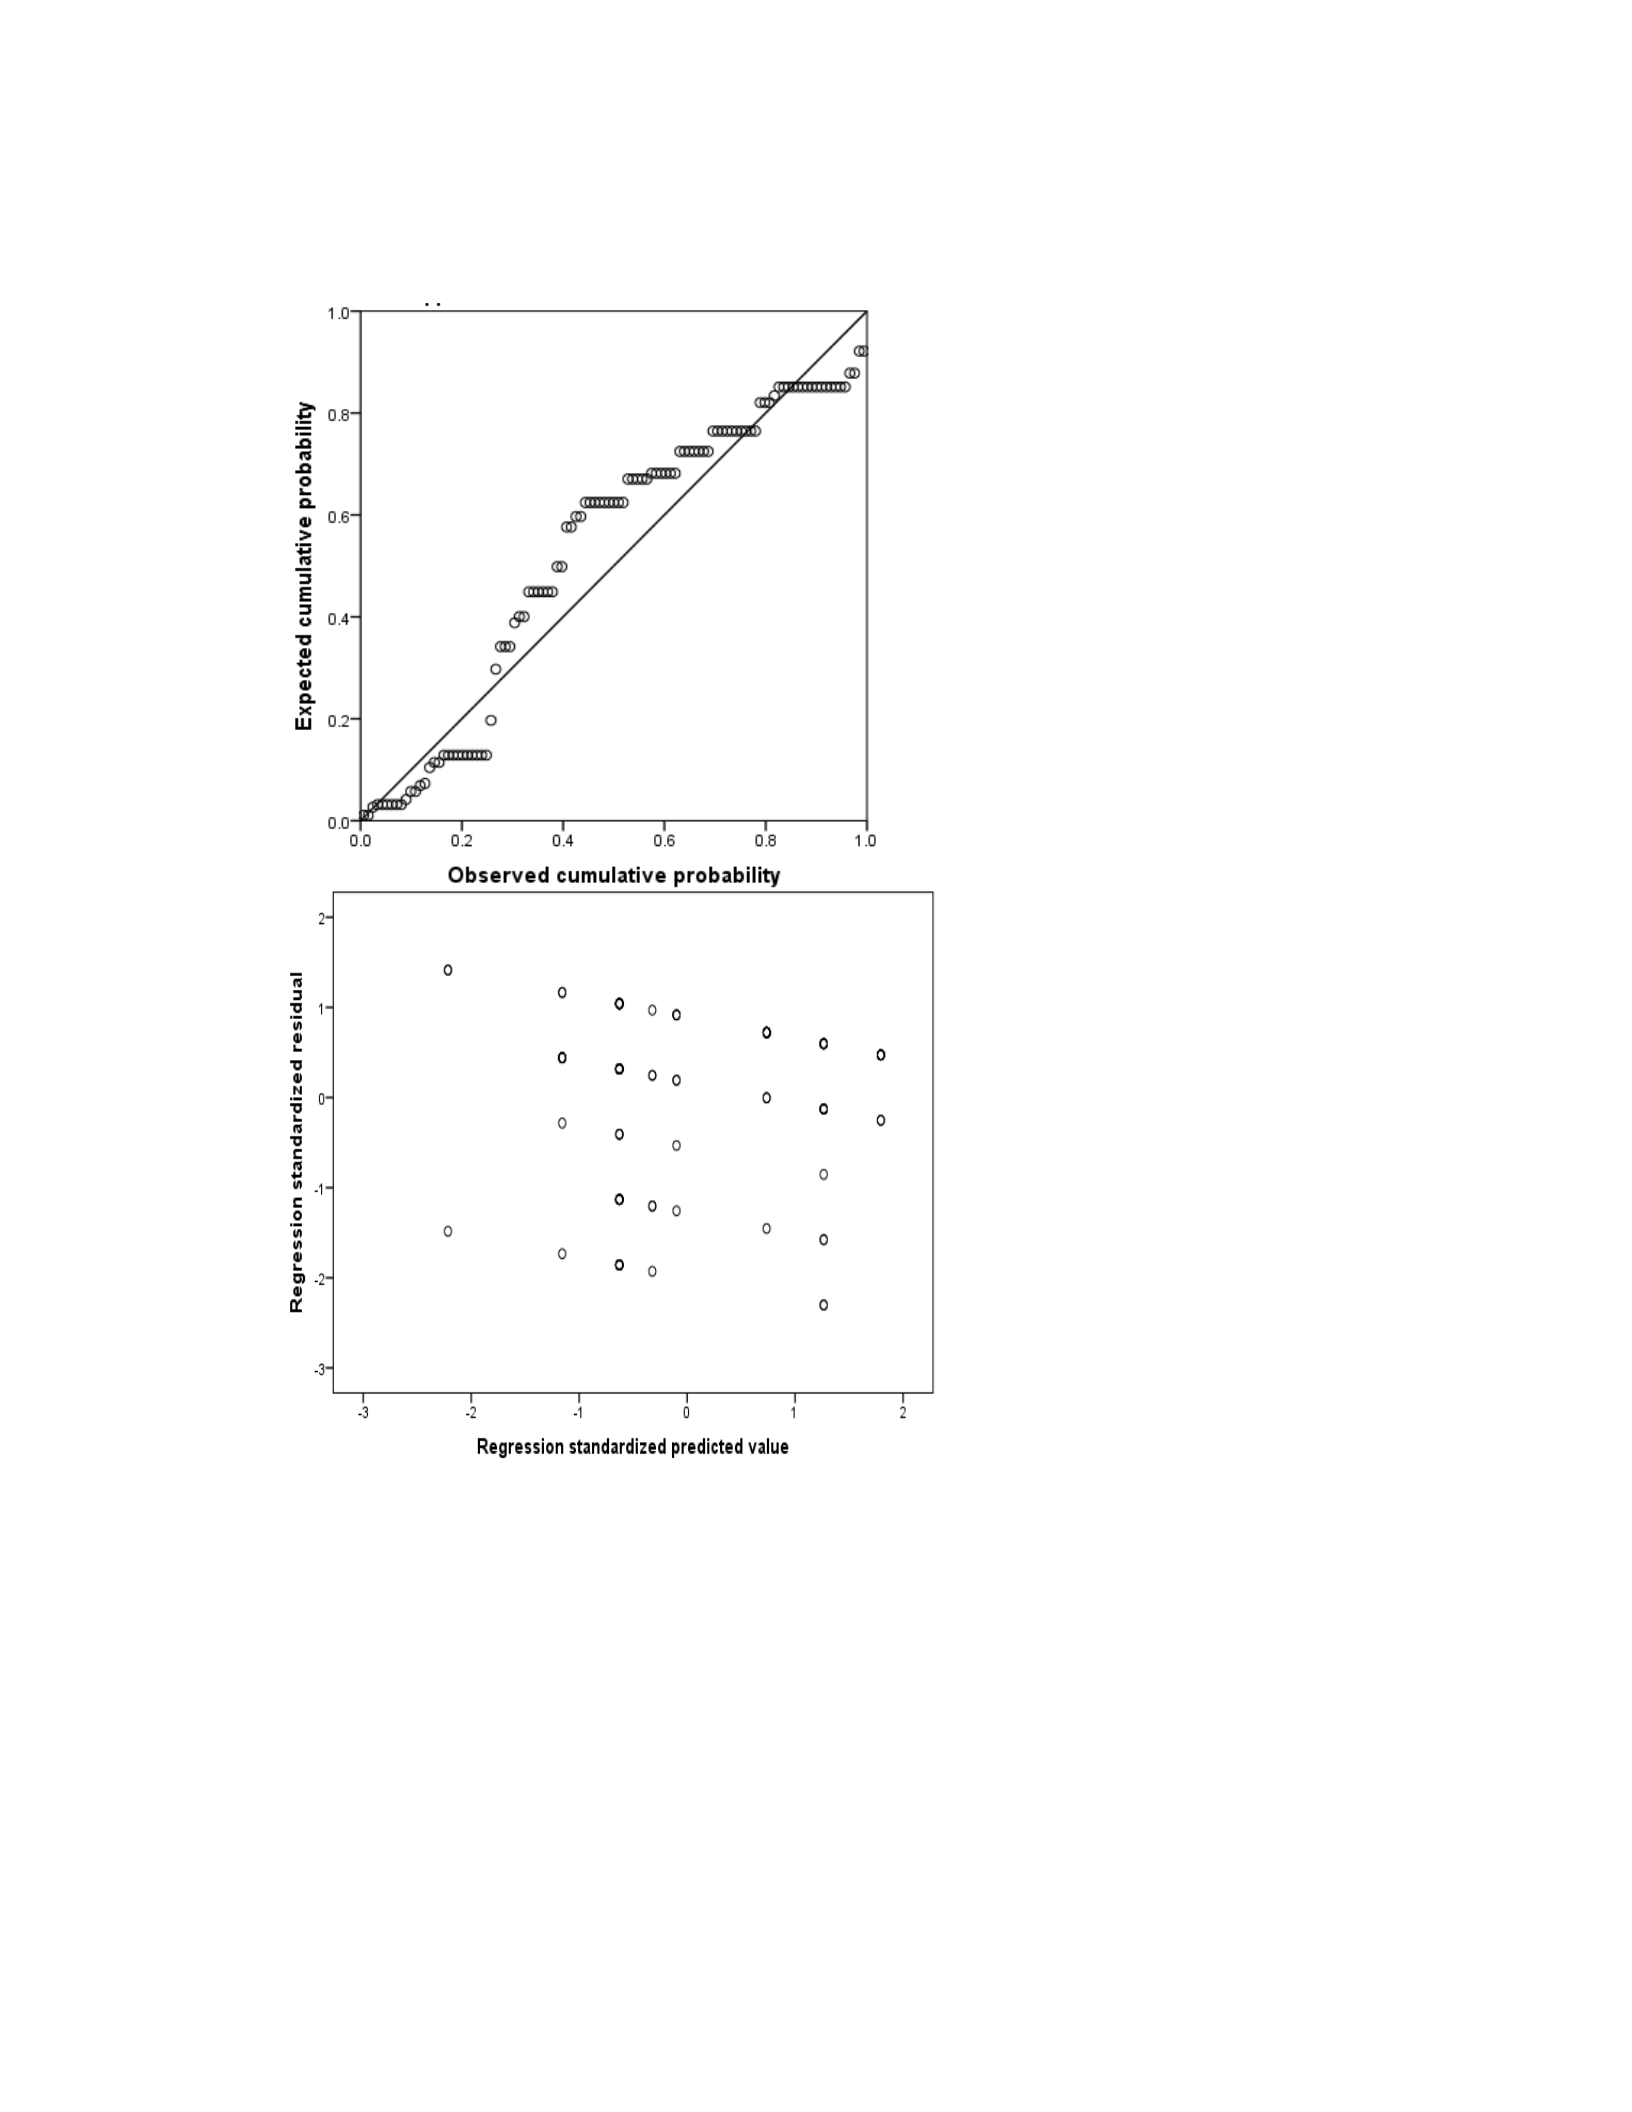
92
Figure 3. Normality and standardized residual scatterplots for Metro Manila.
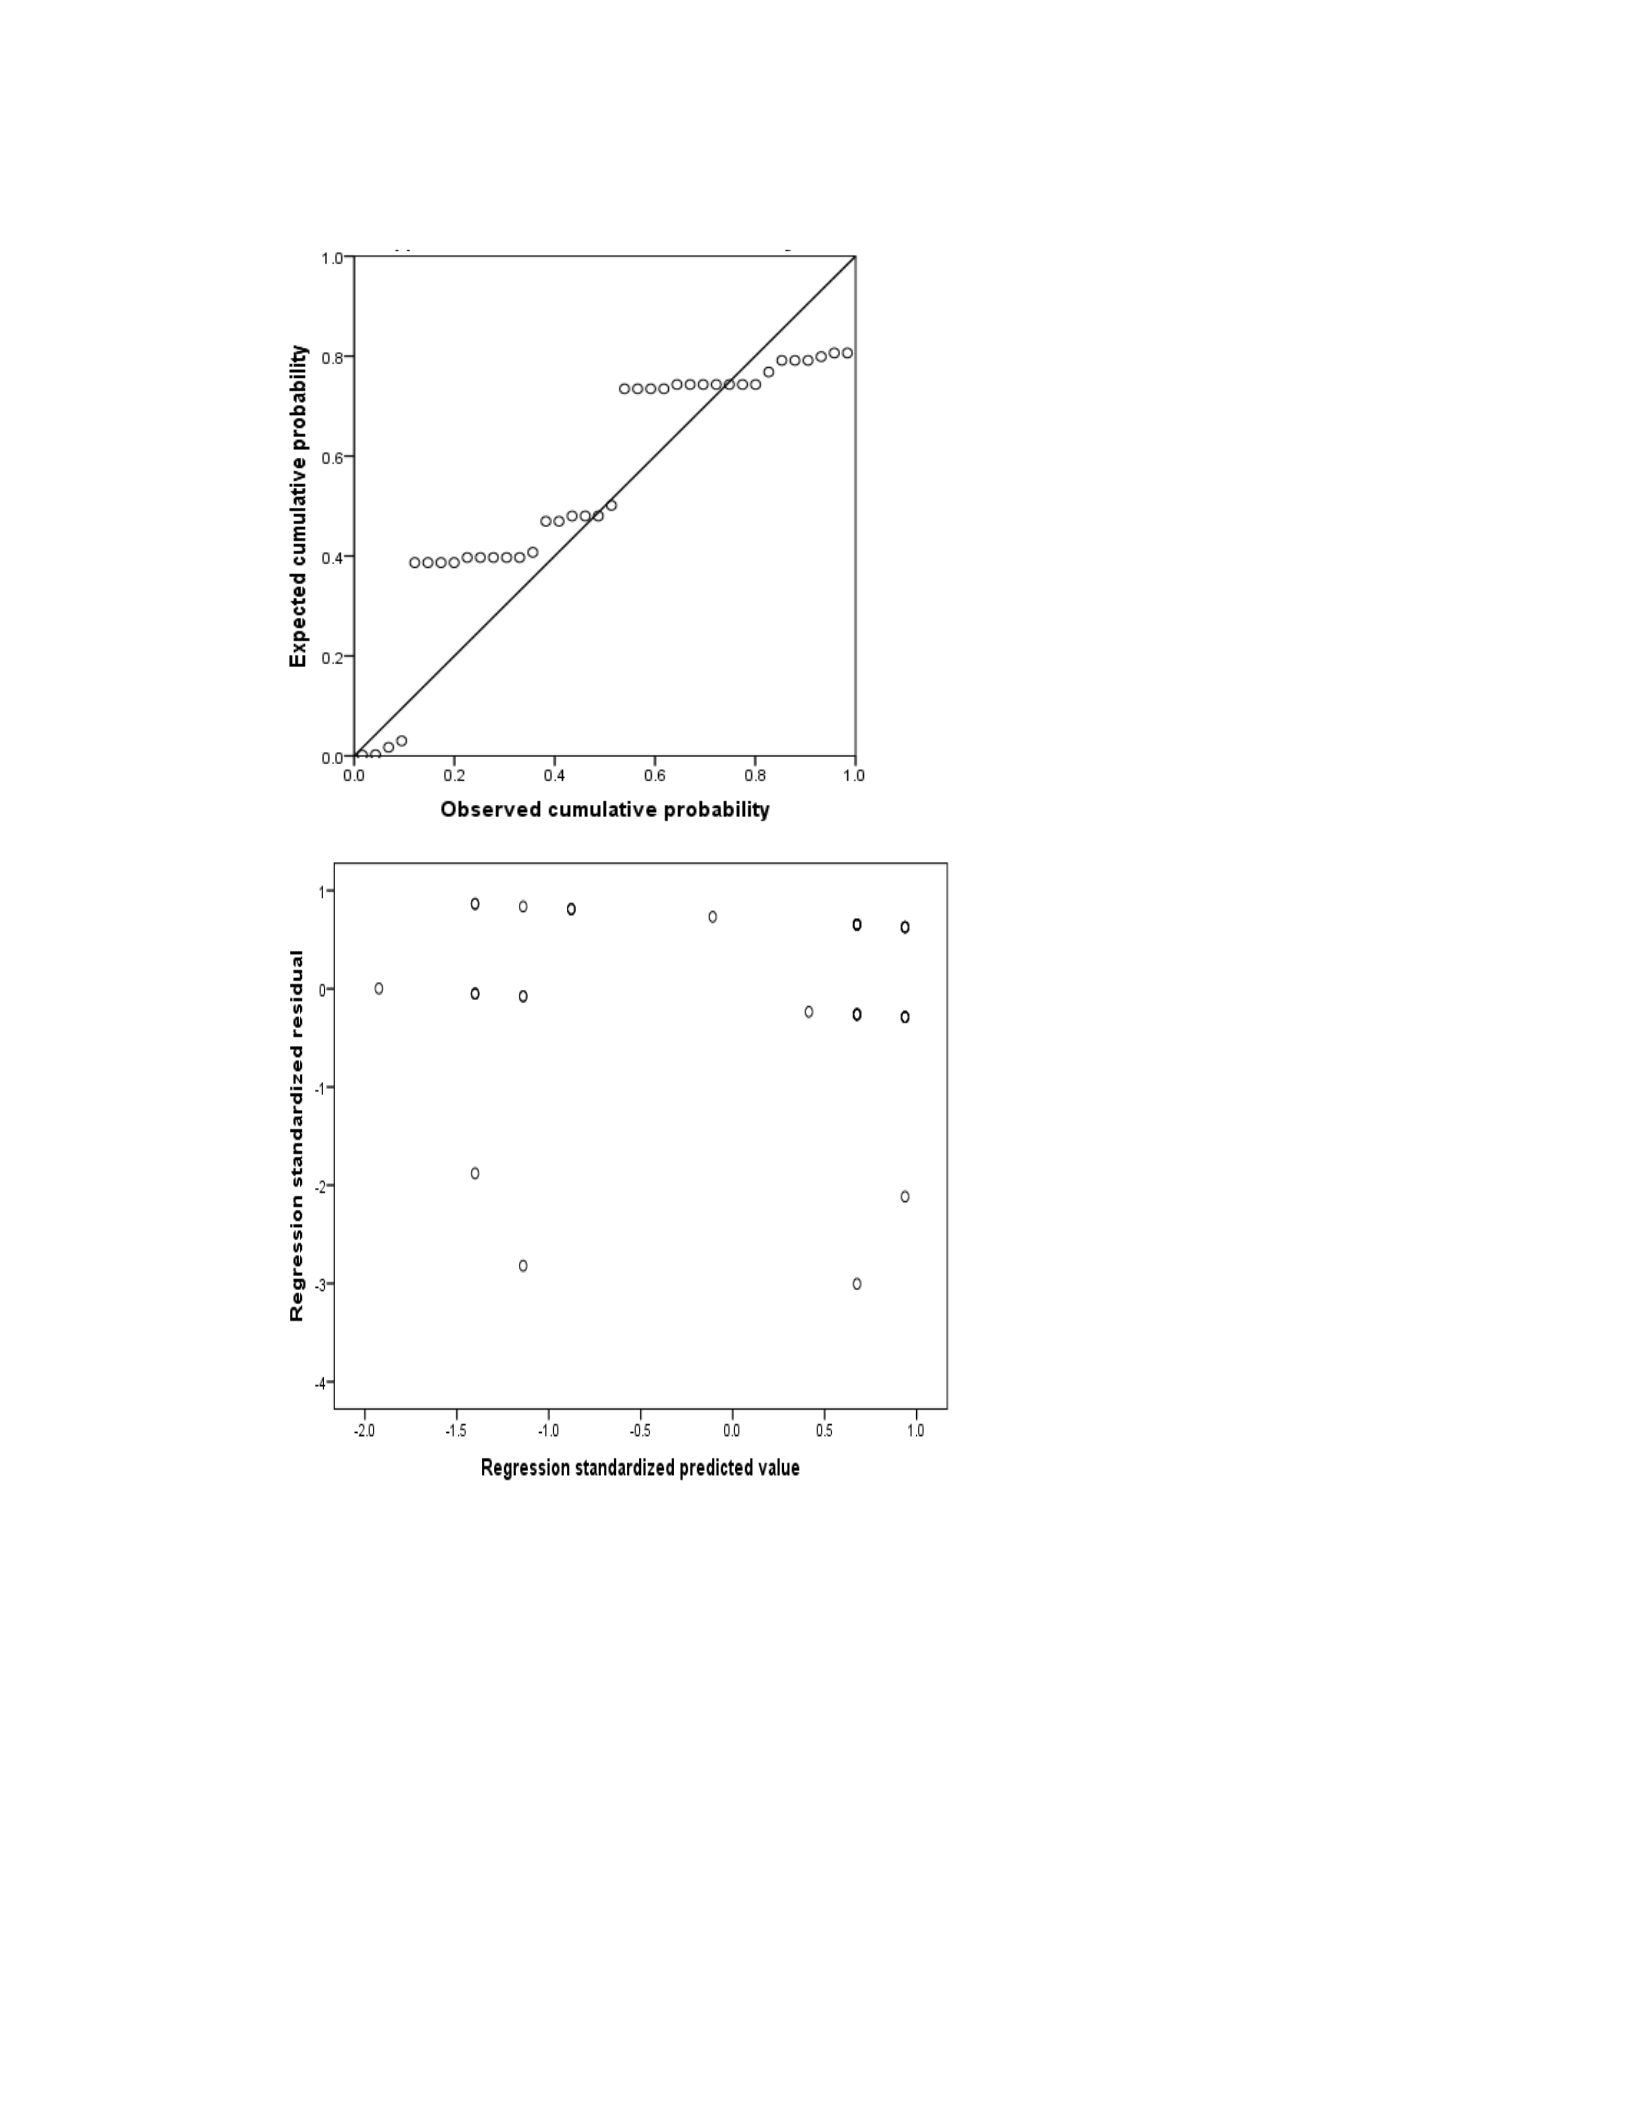
93
Figure 4. Normality and standardized residual scatterplots for Cavite City.
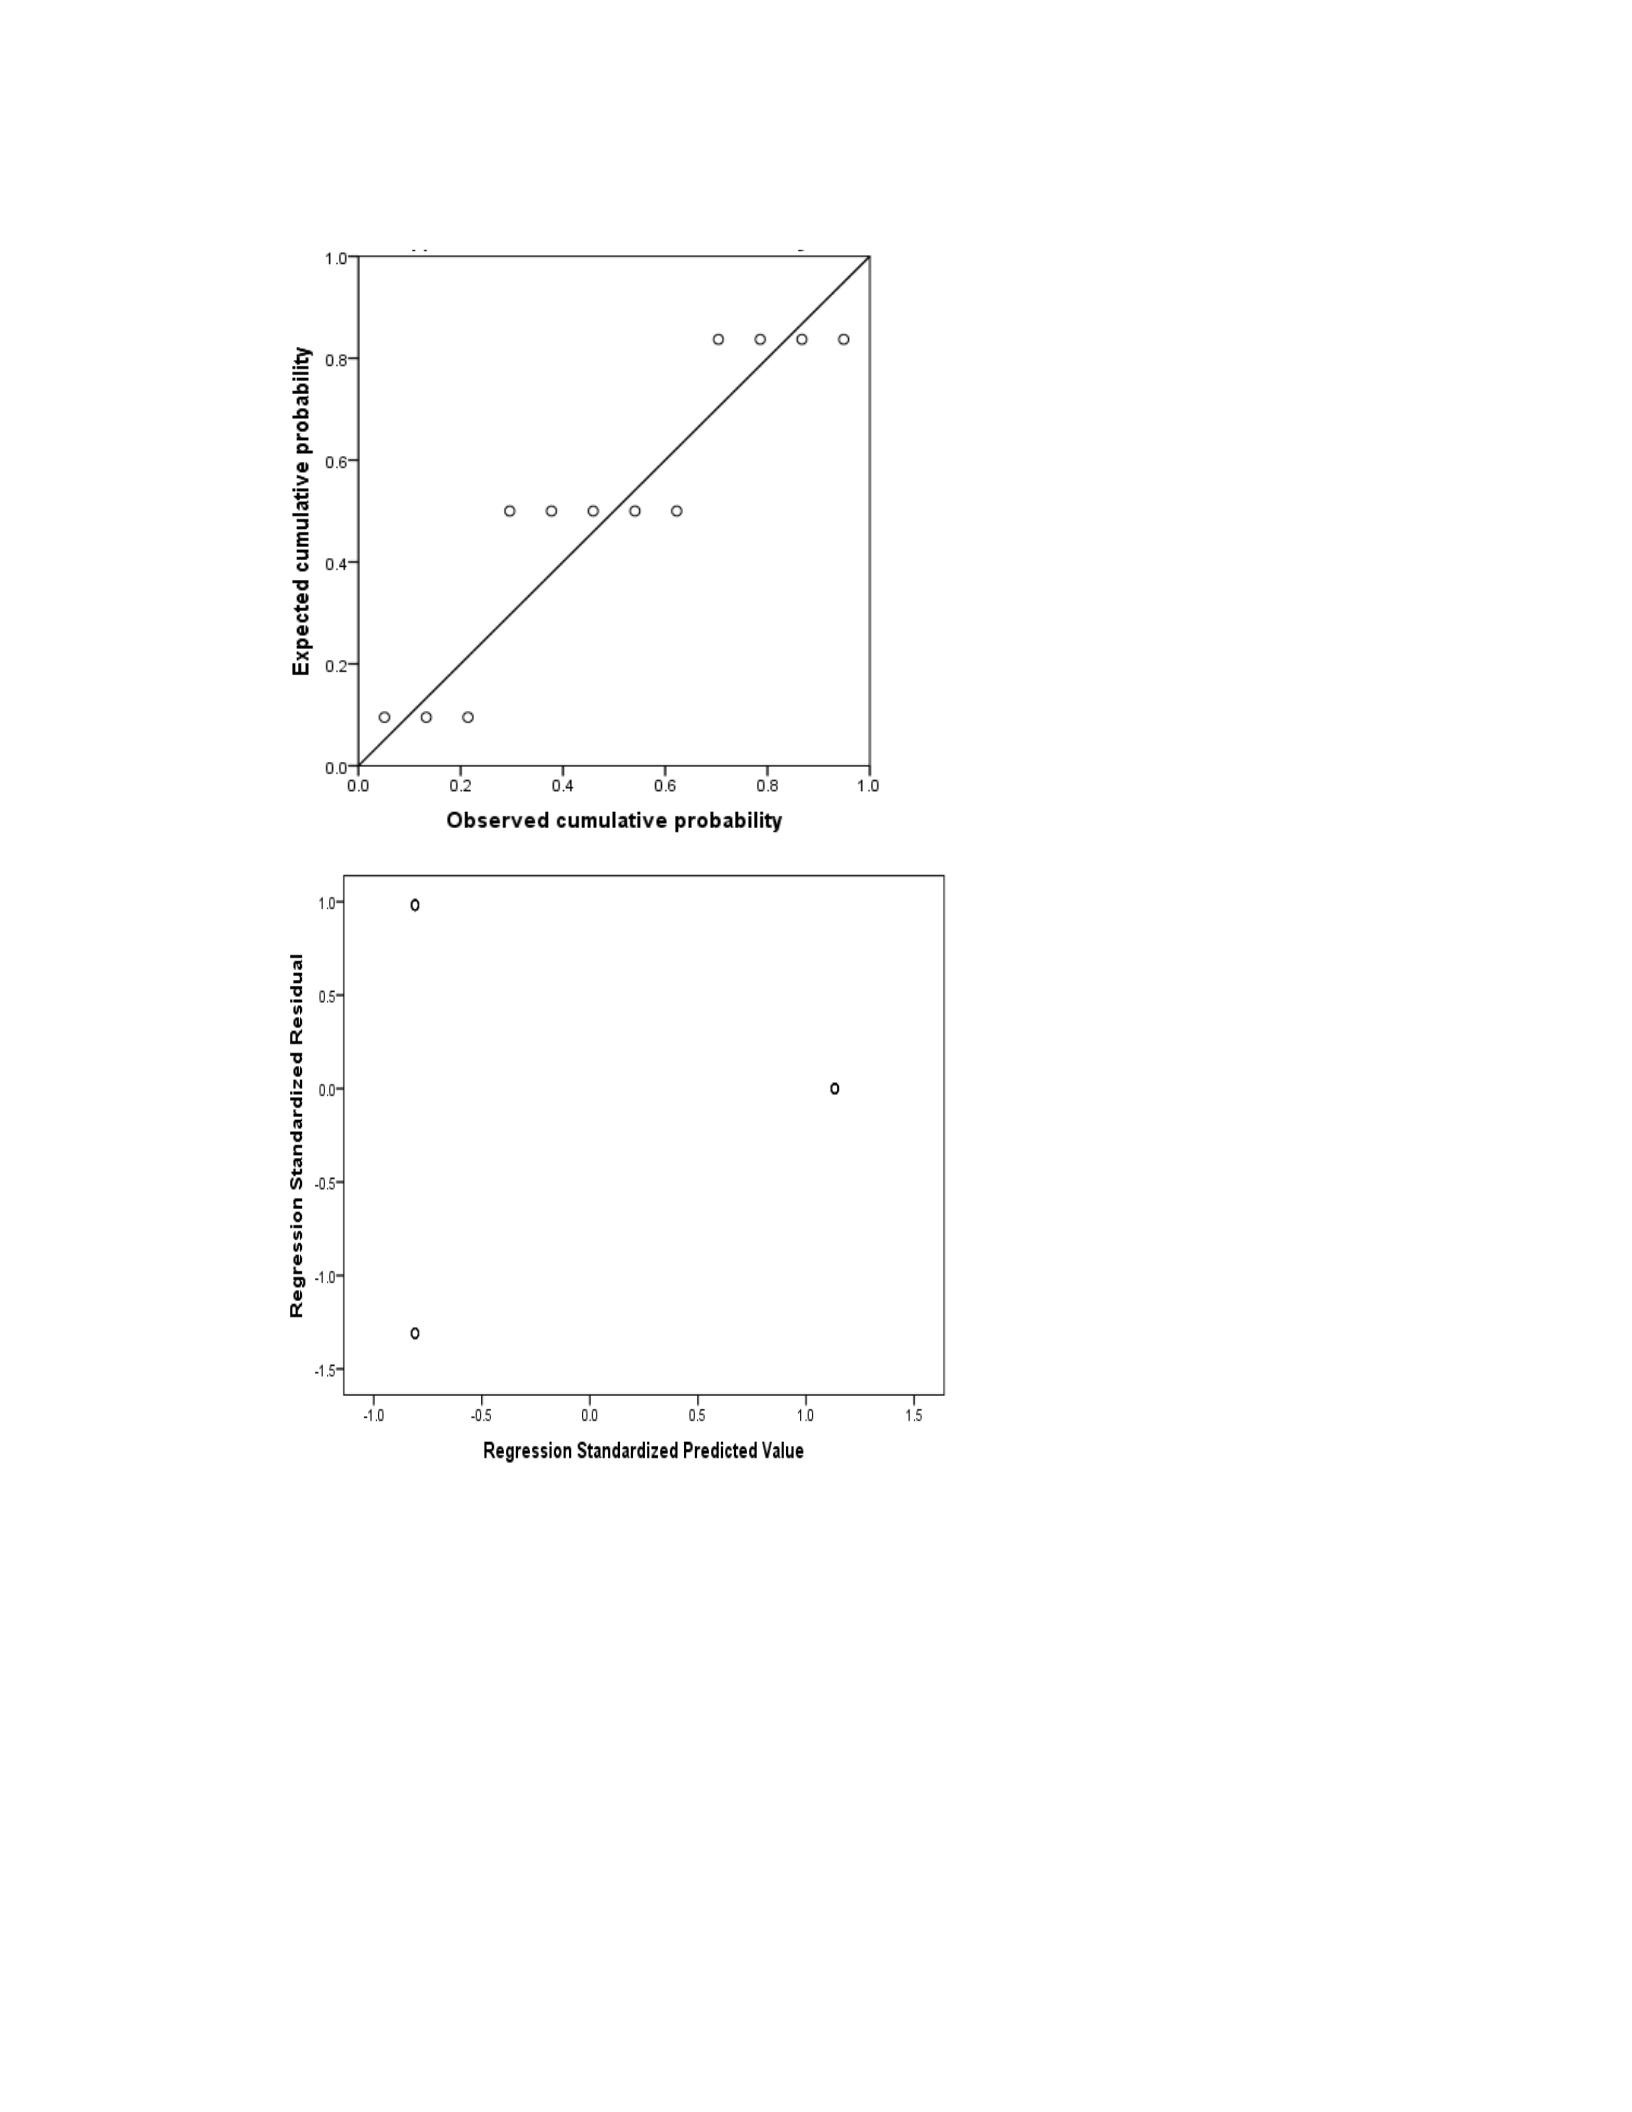
94
Figure 5. Normality and standardized residual scatterplots for Iloilo City.

95
Metro Manila. Results of the first regression were not significant but did
approach significance, F(2,104) = 2.93, p = .058, R2 = .05, suggesting that there is a
possibility for relationships between the independent variables of gender and age and the
dependent variable of health care finder functionality within the Metro Manila
subsample. Again, these findings were not significant, and should not be considered for
interpretation, but they were still examined in an exploratory manner. Assessment of the
individual predictors showed that the only potential influence resulted from
Demonstration recipients’ gender. Though these predictors should not be interpreted due
to the overall regression results, there is some evidence that male Demonstration
recipients were less satisfied with the health care finder functionality, p = .027, B = −.61,
and were .61 units less satisfied on average. No effects were evident from the age
variable. Results of a secondary analysis through binary logistic regression confirmed this
lack of significance (χ2(2) = 4.44, p = .109), and suggested that the nonsignificant
findings were not likely due to the influenced of nonnormality or acquiescence bias.
Cavite City. Results from the second regression were also nonsignificant, F(2,
35) = 0.19, p = .827, R2 = .01, suggesting that there was no evidence for a relationship
between the independent variables of gender and age and the dependent variable of care
finder functionality. Further assessment of the predictor variables supported this lack of
significance. Results of a secondary analysis through binary logistic regression confirmed
this lack of significance (χ2(2) = 0.68, p = .712), and suggested that the nonsignificant
findings were not likely due to the influenced of nonnormality or acquiescence bias.
However, it is possible that these findings were due to the smaller than ideal sample size.

96
Iloilo City. Results from the third regression were also nonsignificant, F(2,9) =
1.41, p = .294, R2 = .24, suggesting that there was no evidence for a relationship between
the independent variables of gender and age and the dependent variable of care finder
functionality. Further assessment of the predictor variables supported this lack of
significance. Results of a secondary analysis through binary logistic regression confirmed
this lack of significance (χ2(2) = 3.94, p = .140), and suggested that the nonsignificant
findings were not likely due to the influenced of nonnormality or acquiescence bias.
However, as with the regression of Cavite City, it is possible that these findings were due
to the smaller than ideal sample size, which was 12 for this regression. Results of these
three subsample regressions can be found in Table 4.
Table 4
Individual Regressions of Care Finder Functionality for each Phase of Demonstration
Source
B
SE
β
t
p
Phase 1: Metro Manila
Gender (ref: female)
−0.61
0.27
−0.22
−2.24
0.027
Age
0.17
0.14
0.12
1.27
0.207
Phase 2: Cavite City, Cavite
Gender (ref: female)
0.20
0.39
0.09
0.52
0.605
Age
0.03
0.19
0.03
0.15
0.879
Phase 3: Iloilo City, Iloilo
Gender (ref: female)
−0.43
0.27
−0.49
−1.57
0.152
Age
0.00
0.49
0.00
0.00
0.999

97
As a follow-up to the regressions conducted to determine the combined predictive
effect of gender and age on health care finder functionality, a final regression was
conducted to examine the effect of these independent variables on satisfaction with
submission of a waiver to request to see a nonapproved provider in a designated
Demonstration location. Within the data set, a total of 33 Demonstration recipients had
requested a waiver and were the only participants to provide data regarding their
satisfaction with this process. Out of these 33, 29 also had data available regarding their
age and gender, which was necessary for use in the regression. These were the only
participants who provided input on the process of submitting such a waiver and were the
only participants used in the regression of waiver submission satisfaction.
Assumption testing again started with an assessment of multicollinearity for this
subsample of 29. With a variance inflation factor value of 1.19, the assumption was met.
As seen in Figure 6, normality slightly deviated from the perfect normal line, which could
be cause for concern when interpreting the results. The residual scatterplot (see Figure 7)
revealed two clusters of responses on the outcome variable, satisfaction with request for a
waiver, though the two clusters were similarly sized and did not indicate problems with
homoscedasticity. The results should nonetheless be considered with caution, as the
normality was questionable and the sample size was not ideal. For this reason, in addition
to these analyses, a binary logistic regressions was conducted in an effort to better
understand the results. This testing took place with the use of a dependent variable
transformed such that zero represented any response less than very satisfied, and one
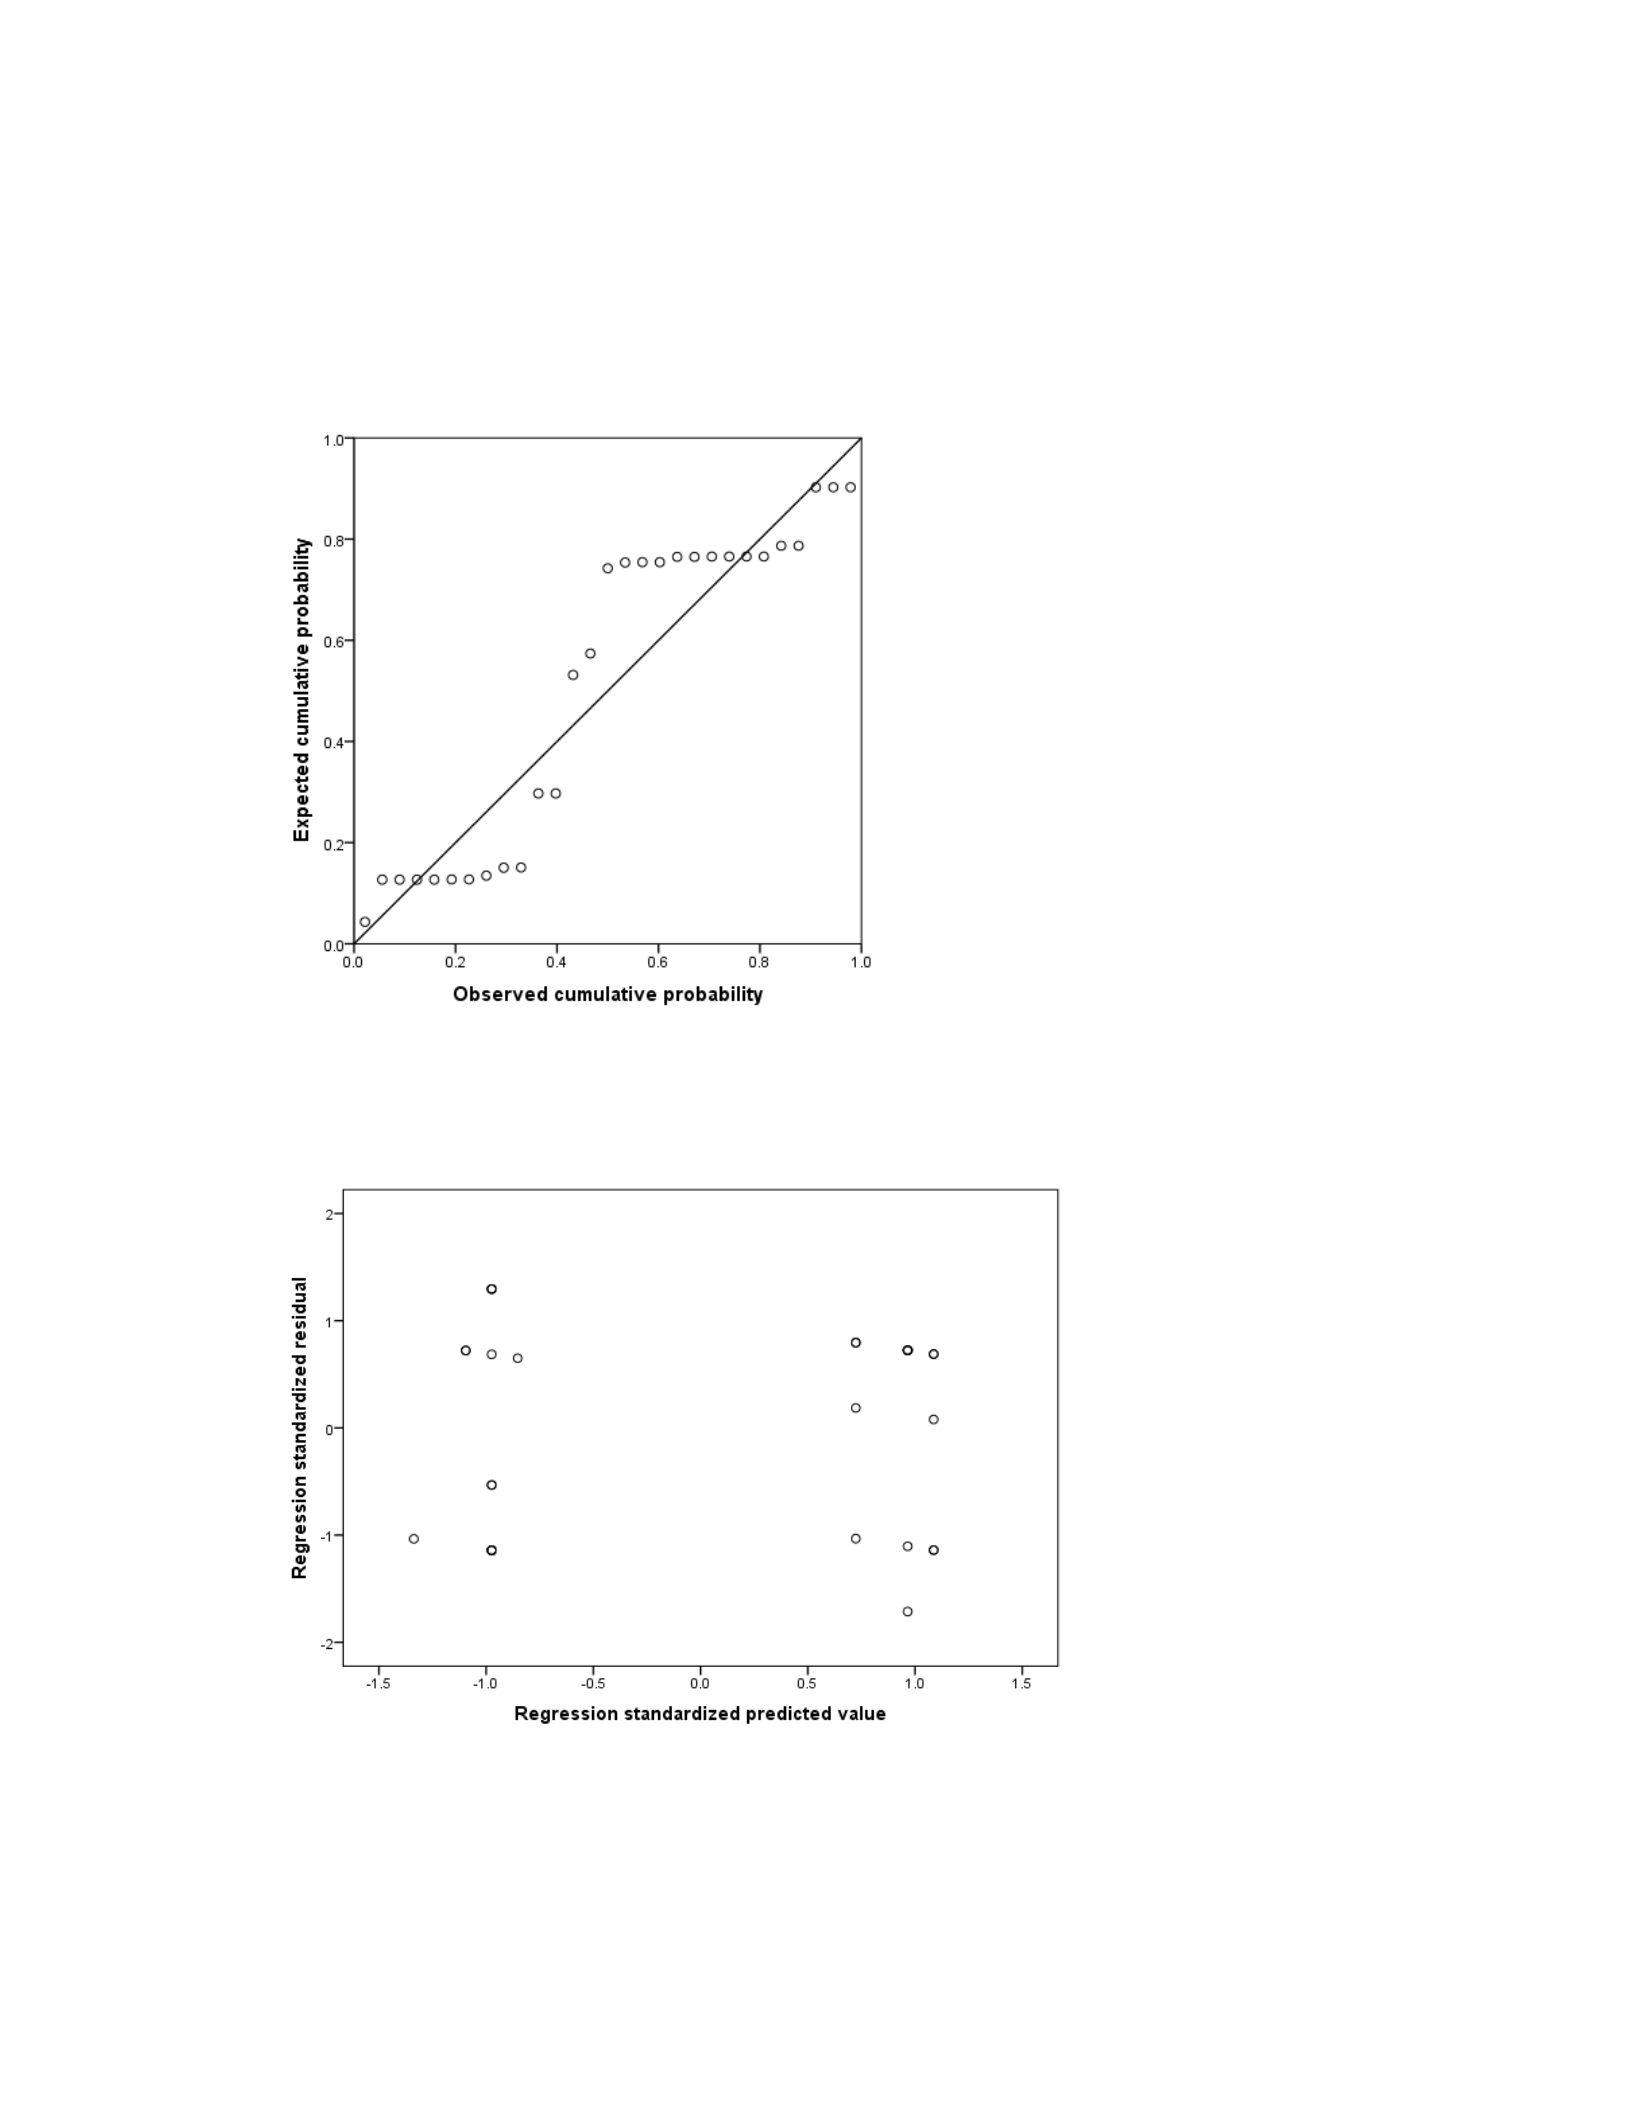
98
represented a response of very satisfied. The binary nature of this variable both addressed
the possibility of acquiescence bias and the non-normal distribution of residuals.
Figure 6. Normal P-P plot for regression satisfaction with waiver.
Figure 7. Standardized residual plot for regression of satisfaction with waiver.

99
Results of this final regression were also nonsignificant, F(2,26) = 1.22, p = .313,
R2 = .09, and provided no evidence for a relationship between a Demonstration
recipient’s gender or age and his or her satisfaction with request for a waiver. Subsequent
testing through a binary logistic regression provided similar results (χ2(2) = 2.75, p
= .253), indicating no evidence for a relationship between the predictors of gender and
age and the outcome of satisfaction with the request for a waiver. Because these results
were not significant, the individual predictors should not be examined further; however, a
quick visual assessment of the two predictors confirms the overall findings. These results
can be found in Table 5.
Table 5
Regression of Satisfaction With Waiver on Gender and Age
Source
B
SE
β
t
p
Gender (ref: female)
−0.99
0.67
−0.31
−1.50
0.147
Age
0.06
0.29
0.04
0.20
0.844
Research Question 3
RQ3: What is the relationship between a closed network, actual beneficiary out-
of-pocket cost, and quality health care in Demonstration areas?
H03a: There is no statistically significant relationship between actual
beneficiary cost and a closed provider network.
Ho3a: There is a statistically significant relationship between actual
beneficiary out-of-pocket cost and a closed provider network.

100
H03b: There is no statistically significant relationship between quality health
care and a closed provider network.
Ha3b: There is a statistically significant relationship between quality health
care and a closed provider network.
To examine RQ3, three questions from the survey were chosen as representations
of the beneficiary out-of-pocket costs and quality health care. The first question asked
participants to rate their out-of-pocket costs in relation to those same costs prior to the
Demonstration. As seen in Table 6, most felt that their costs were either higher now
(36.1%) or about the same (35.6%), with a minority reporting lower costs following the
Demonstration (10.0%). To examine the quality of health care, participants were asked to
rate their satisfaction on a scale from 0 to 10. As seen in Table 6, many responded with a
score of 5 or above. Finally, participants were asked to compare their current experience
with receiving health care to their experience before, and the two largest response groups
consisted of those who felt their experience was about the same (28.9%) or much better
(29.4%). However, to test whether these responses were significantly higher or lower
than their mid-level response categories, a series of one-sample t-tests was conducted.

101
Table 6
Responses to Questions Regarding Beneficiary Cost and Quality Health Care
Response
n
%
Out-of-pocket expenses following Demonstration
Higher now
65
36.1
About the same now
64
35.6
Lower now
18
10.0
No response
33
18.3
Rating of satisfaction with health care quality where 0 is worse and 10 is best possible
0
9
5.0
1
3
1.7
2
4
2.2
3
4
2.2
4
8
4.4
5
14
7.8
6
9
5.0
7
27
15.0
8
47
26.1
9
24
13.3
10
30
16.7
No response
1
0.6
Comparison of current experience receiving healthcare before Demonstration
(1) Much worse
21
11.7
(2) Somewhat worse
17
9.4
(3) About the same
52
28.9
(4) Somewhat better
19
10.6
(5) Much better
53
29.4
No response
18
10.0

102
Each of these three questions was first assessed to determine which response
category would take the role of comparison value. For out-of-pocket expenses, the
category of about the same now was chosen, and results would thus indicate whether
participants responded with a significantly higher or lower value on average. Similarly,
the rating of 5 was chosen for the rating between 1 and 10, as this indicated a middle
response, and testing would thus indicate whether participants responded significantly
higher or lower than the objective middle category. For the last question, which asked
participants to compare their experience receiving health care before and after the
Demonstration, the category of about the same was chosen, as results would thus indicate
whether participants tended to respond close to the much worse or much better anchor of
the scale. Examination of the distribution for responses to all three of these items
indicated no evidence of acquiescence bias or skewed distributions, suggesting that there
was no need for a binary transformation, and that t tests would be the best suited method
for statistical analysis.
Results for all three tests were significant, indicating that participant responses
tended to be significantly different from their middle response categories. The responses
to out-of-pocket expenses compared to a value of 2, or about the same were significant at
the p < .001 level, t(146) = −5.68. Examination of the mean difference showed that
participants tended to respond that the expenses were higher now with a frequency more
common than would be expected at random. However, the satisfaction value with
response categories ranging from 0 to 10 also consisted of responses significantly
different from the middle response of 5. This difference was also significant at the p <
103
.001 level, t(178) = 15.27. Results of this analysis showed that the Demonstration
recipients tended to respond an average of 3.04 units higher than the middle response of
5, suggesting that they responded significantly closer to the best possible anchor of the
satisfaction scale. Finally, the comparison of satisfaction from before to after the
Demonstration was also significant at the p < .001 level, t(162) = 3.77. Examination of
the mean difference between the sample’s responses and the response of about the same
showed that participants responded significantly higher, or closer to the much better
anchor of this scale. See Table 7.
Table 7
One-Sample t Tests for Expenses and Satisfaction Following Demonstration
Variable
t (df)
p
Mean difference
Out-of-pocket expenses
−5.68 (146)
<0.001
−0.32
Satisfaction (0–10)
15.27 (178)
<0.001
3.04
Satisfaction compared to predemonstration
3.77 (162)
<0.001
0.41
Beneficiary Actual Out-of-Pocket Costs
How much were the actual out-of-pocket costs for beneficiaries for calendar years
(CYs) 2011, 2012, 2013, 2014, and 2015 in Metro Manila, Cavite City, Cavite, and Iloilo,
Iloilo? Prior to the Philippine Demonstration, beneficiaries paid a deductible and cost
share plus balance billing. After the implementation of the Philippine Demonstration,
beneficiaries paid a deductible and cost share. There is an assumption that beneficiaries’
overall out-of-pocket costs would increase initially because greater than half the
TRICARE beneficiaries were not using the TRICARE benefit. As more beneficiaries use

104
the TRICARE benefit and receive care from approved Demonstration providers, their
costs should eventually show a decrease.
To evaluate beneficiary actual out-of-pocket costs, an analysis of claims data from
January 1, 2011, through December 31, 2015, was conducted to assess the impact of the
Philippine Demonstration on beneficiary financial burden comparing beneficiary out-of-
pocket cost prior to the Philippine Demonstration and during the Philippine
Demonstration. All numbers for the analysis were rounded, less than .50 were rounded
down, and .50 and higher were rounded up.
The analysis was based on CYs January 1, 2011, through December 31, 2015.
This analysis was based on Phase 1 Metro Manila and its surrounding areas, Phase 2
Cavite City, Cavite, and Phase 3, Iloilo City, Iloilo. An analysis of the claims data from
January 1, 2011, through December 31, 2012, used the same locations selected for the
Philippine Demonstration and analyzed using special processing codes: Special
Processing Code 1, Special Processing Code 2, Special Processing Code 3, and Special
Processing Code 4. To protect the identities of TRICARE beneficiaries, the 18 categories
of HIPAA identifiers were removed. Therefore all personally identifiable information
was removed from the claims data.
Inpatient Beneficiary Out-of-Pocket Costs
Table 8 and Figure 8 show the grand total for inpatient beneficiary out-of-pocket
costs using all special processing codes for CY 2011 as $147, 320, CY 2012 as $143,
682, CY 2013 as $140, 224, CY 2014 as $223, 820, and CY 2015 as $231,506. A closer
examination of the inpatient beneficiary out-of-pocket costs for Phase I for Metro Manila
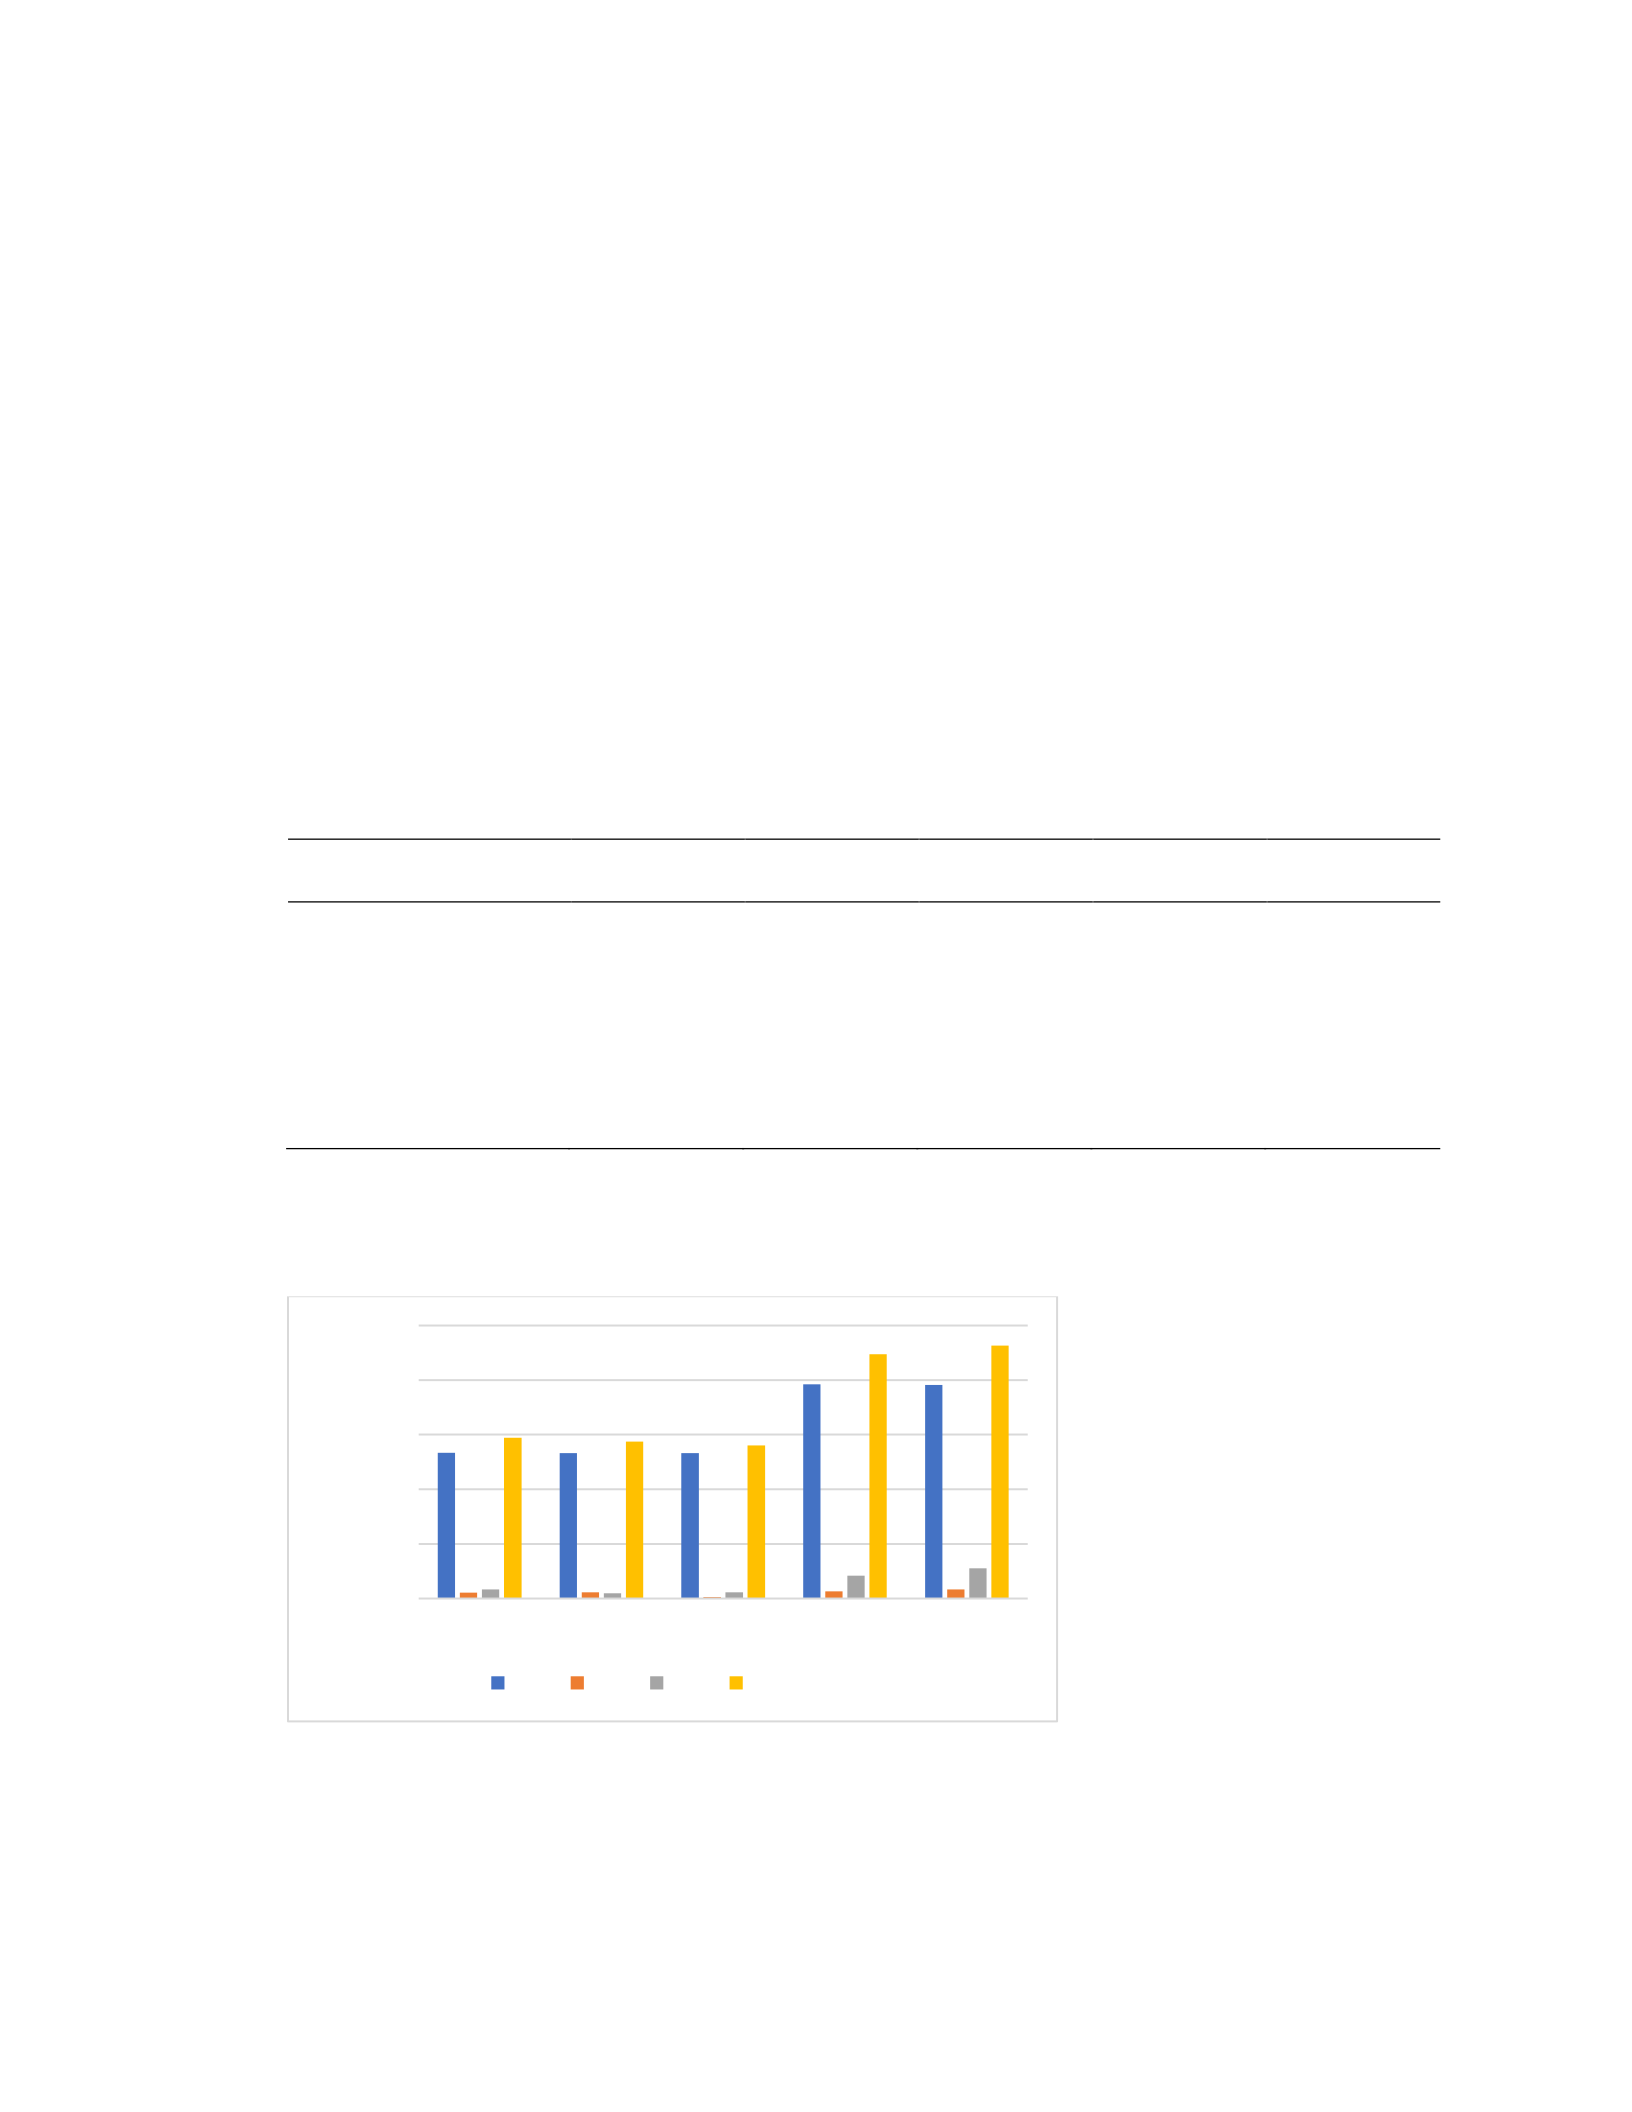
105
shows beneficiaries out-of-pocket costs for CY 2011 as $133,510, CY 2012 as $133,276,
CY 2013 as $133,192, CY 2014 as $196,199, and CY 2015 as $195,521. Phase 2 for
Cavite City, Cavite, shows beneficiaries’ out-of-pocket costs for CY 2011 as $5,440, CY
2012 as $5,672, CY 2013 as $1,347, CY 2014 as $6,626, and CY 2015 as $8,386. Phase
3 for Iloilo City, Iloilo, shows beneficiaries’ out-of-pocket costs for CY 2011 as $8,371,
CY 2012 as $4,733, CY 2013 as $5,684, CY 2014 as $20,995, and CY 2015 as $27,598.
Table 8
Inpatient Beneficiary Out-of-Pocket Costs All Special Processing Code
Demo city/phase
CY2011
CY2012
CY2013
CY2014
CY2015
PH1
$133,510
$133,276
$133,192
$196,199
$195,521
PH2
$5,440
$5,672
$1,347
$6,626
$8,386
PH3
$8,371
$4,733
$5,684
$20,995
$27,598
Grand total
$147,320
$143,682
$140,224
$223,820
$231,506
Figure 8. Inpatient beneficiary out-of-pocket costs all special processing code.
$0
$50,000
$100,000
$150,000
$200,000
$250,000
CY2011 CY2012 CY2013 CY2014 CY2015
PH1 PH2 PH3 Grand Total

106
Table 9 and Figure 9 show the grand total for inpatient beneficiary out-of-pocket
costs for using Special Processing Code PH for CY 2011 as $0, CY 2012 as $0, CY 2013
as $65,529, CY 2014 as $172,507, and CY 2015 as $184,158. For Table 9, the dollar
value for CY 2011 and CY 2012 will not be discussed because the Demonstration had not
commenced and claims were not processed using Special Processing Code PH. Phase I
for Metro Manila shows beneficiaries’ out-of-pocket costs for CY 2013 as $63,911, CY
2014 as $149,911, and CY 2015 as $149,014. Phase 2 for Cavite City, Cavite, shows
beneficiaries’ out-of-pocket costs for CY 2013 as $196, CY 2014 as $6,162, and CY
2015 as $8,103. Phase 3 for Iloilo, Iloilo, shows beneficiaries’ out-of-pocket costs for CY
2013 as $1,422, CY 2014 as $16,435, and CY 2015 as $27,041.
Table 9
Inpatient Beneficiary Out-of-Pocket Costs With Special Processing Code PH
Demo city/phase
CY2011
CY2012
CY2013
CY2014
CY2015
PH1
$0
$0
$63,911
$149,911
$149,014
PH2
$0
$0
$196
$6,162
$8,103
PH3
$0
$0
$1,422
$16,435
$27,041
Grand total
$0
$0
$65,529
$172,507
$184,158
107
Figure 9. Inpatient beneficiary out-of-pocket costs with Special Processing Code PH.
Table 10 and Figure 10 show the difference between Table 8 and Table 9 for
inpatient beneficiary out-of-pocket costs, keeping in mind there is no difference for CY
2011 and CY 2012 because the Philippine Demonstration had not been implemented.
Thus the grand total for inpatient beneficiary out-of-pocket costs difference for CY 2013
is $74,695, CY 2014 is $51,312, and CY 2015 is $47,347. Phase 1 for Metro Manila
shows a difference for inpatient beneficiary out-of-pocket costs for CY 2013 as $133,192,
CY 2014 as $196,199, and CY 2015 as $195,521. Phase 2 for Cavite City, Cavite,
difference in out-of-pocket costs for CY 2013 is $1,152, CY 2014 is $464, and CY 2015
is $283. Phase 3 for Iloilo City, Iloilo, difference in out-of-pocket costs for CY 2013 is
$4,262, CY 2014 is $4,560, and CY 2015 is $557.
$0
$50,000
$100,000
$150,000
$200,000
CY2011 CY2012 CY2013 CY2014 CY2015
PH1 PH2 PH3 Grand Total
108
Table 10
Difference of Inpatient Beneficiary Out-of-Pocket Cost for Table 8 and Table 9
Demo city/phase
CY2011
CY2012
CY2013
CY2014
CY2015
PH1
$133,510
$133,276
$69,282
$46,288
$46,507
PH2
$5,440
$5,672
$1,152
$464
$283
PH3
$8,371
$4,733
$4,262
$4,560
$557
Grand total
$147,320
$143,682
$74,695
$51,312
$47,347
Figure 10. Difference of inpatient beneficiary out-of-pocket cost for Table 8 and Table 9.
Outpatient Beneficiary Out-of-Pocket Costs
Table 11 and Figure 11 show the grand total for outpatient beneficiary out-of-
pocket costs using all special processing codes for CY 2011 as $368,029, CY 2012 as
$232,041, CY 2013 as $187,933, CY 2014 as $197,438, and CY 2015 as $218,544. An
examination of the outpatient beneficiary out-of-pocket costs for Phase 1 for Metro
Manila shows beneficiaries’ out-of-pocket costs for CY 2011 as $211,087, CY 2012 as
$0
$20,000
$40,000
$60,000
$80,000
$100,000
$120,000
$140,000
$160,000
CY2011 CY2012 CY2013 CY2014 CY2015
PH1 PH2 PH3 Grand Total
109
$169,253, CY 2013 as $130,576, CY 2014 as $154,243, and CY 2015 as $175,780. Phase
2 for Cavite City, Cavite, shows beneficiaries’ out-of-pocket costs for CY 2011 as
$144,960, CY 2012 as $45,562, CY 2013 as $37,870, CY 2014 as $15,286, and CY 2015
as $15,025. Phase 3 for Iloilo City, Iloilo, shows beneficiaries out-of-pocket costs for CY
2011 as $11,983, CY 22012 as $17,225, CY 2013 as $19,487, CY 2014 as $27,909, and
CY 2015 as $27,740.
Table 11
Outpatient Beneficiary Out-of-Pocket Costs Including Special Processing Code PH
Demo city/phase
CY2011
CY2012
CY2013
CY2014
CY2015
PH1
$211,087
$169,253
$130,576
$154,243
$175,780
PH2
$144,960
$45,562
$37,870
$15,286
$15,025
PH3
$11,983
$17,225
$19,487
$27,909
$27,740
Grand total
$368,029
$232,041
$187,933
$197,438
$218,544
Figure 11. Outpatient beneficiary out-of-pocket costs including special processing code.
$0
$50,000
$100,000
$150,000
$200,000
$250,000
$300,000
$350,000
$400,000
CY2011 CY2012 CY2013 CY2014 CY2015
PH1 PH2 PH3 Grand Total

110
Table 12 and Figure 12 show the grand total for outpatient beneficiary out-of-
pocket costs for using Special Processing Code PH for CY 2011 as $0, CY 2012 as $0,
CY 2013 as $91,521, CY 2014 as $157,590, and CY 2015 as $192,797. For Table 12, the
dollar value for CY 2011 and CY 2012 will not be discussed because the Demonstration
had not commenced and claims were not processed using Special Processing Code PH.
Phase 1 for Metro Manila shows beneficiaries’ out-of-pocket costs for CY 2013 as
$89,100, CY 2014 as $127,467, and CY 2015 as $152,897. Phase 2 for Cavite City,
Cavite, shows beneficiaries’ out-of-pocket costs for CY 2013 as $992, CY 2014 as
$13,541, and CY 2015 as $14,173. Phase 3 for Iloilo City, Iloilo, shows beneficiaries’
out-of-pocket costs for CY 2013 as $1429, CY 2014 as $16,581, and CY 2015 as
$25,727.
Table 12
Outpatient Beneficiary Out-of-Pocket Costs With Special Processing Code PH
Demo city/phase
CY2011
CY2012
CY2013
CY2014
CY2015
PH1
$0
$0
$89,100
$127,467
$152,897
PH2
$0
$0
$992
$13,541
$14,173
PH3
$0
$0
$1,429
$16,581
$25,727
Grand total
$0
$0
$91,521
$157,590
$192,797
111
Figure 12. Outpatient beneficiary out-of-pocket costs with Special Processing Code PH.
Table 13 and Figure 13 show the difference between Table 11 and Table 12 for
outpatient beneficiary out-of-pocket costs, keeping in mind there is no difference for CY
2011 and CY 2012 because the Philippine Demonstration had not been implemented.
Thus the grand total for inpatient beneficiary out-of-pocket costs difference for CY 2013
is $96,412, CY 2014 is $39,848, and CY 2015 is $23,747. Phase 1 for Metro Manila
shows a difference for inpatient beneficiary out-of-pocket costs for CY 2013 as $41,476,
CY 2014 as $26,775, and CY 2015 as $22,882. Phase 2 for Cavite City, Cavite,
difference in out-of-pocket costs for CY 2013 is $36,879, CY 2014 is $41,745, and CY
2015 is $852. Phase 3 for Iloilo City, Iloilo, difference in out-of-pocket costs for CY
2013 is $18,058, CY 2014 is $11,328, and CY 2015 is $2,013.
$0
$50,000
$100,000
$150,000
$200,000
$250,000
CY2011 CY2012 CY2013 CY2014 CY2015
PH1 PH2 PH3 Grand Total
112
Table 13
Difference of Outpatient Beneficiary Out-of-Pocket Cost
Demo city/phase
CY2011
CY2012
CY2013
CY2014
CY2015
PH1
$211,087
$169,253
$41,476
$26,775
$22,882
PH2
$144,960
$45,562
$36,879
$1,745
$852
PH3
$11,983
$17,225
$18,058
$11,328
$2,013
Grand total
$368,029
$232,041
$96,412
$39,848
$25,747
Figure 13. Difference of outpatient beneficiary out-of-pocket cost.
Summary
Chapter 4 contained the statistical findings resulting from an examination of the
survey responses from Metro Manila, Cavite, and Iloilo. The findings centered on three
RQs and an analysis of claims data organized as such. Results of the three RQs provided
evidence for a positive relationship between Demonstration recipients’ financial burdens
$0
$50,000
$100,000
$150,000
$200,000
$250,000
$300,000
$350,000
$400,000
CY2011 CY2012 CY2013 CY2014 CY2015
PH1 PH2 PH3 Grand Total

113
and satisfaction with the Demonstration as well as their confidence that their health care
needs would be met. However, when assessing age and gender, there was little evidence
to suggest that Demonstration recipients had different opinions of the health care finder
functionality or satisfaction requesting a waiver based on their age or gender. Conversely,
this indicated that men and women of all ages were similarly satisfied with the health
care finder functionality and ability to receive a waiver to contact a nonapproved
Demonstration provider. The results also showed that participants were highly satisfied
with the Demonstration overall and were much more satisfied with their health care
following the Demonstration. However, these same participants also felt that their out-of-
pocket expenses were higher than before the Demonstration. An analysis of the claims
data for the beneficiary out-of-pocket costs for inpatient and outpatient care showed that
the beneficiaries’ out-of-pocket costs increased in demonstration areas and decreased in
non-demonstration areas; thus, indicating a preference for a closed network. In Chapter 5,
these findings will be explored in terms of what is already known, compared to my
expectations, and assessed for interpretation and suggestions for further research.

114
Chapter 5: Discussion, Conclusion, and Recommendations
Introduction
The aim of this research was to examine the efficacy and acceptability of
employing an alternative method for the delivery of health care by increasing access and
reducing beneficiary out-of-pocket costs while maintaining quality health care. The DHA
implemented a closed network under the DoD TRICARE Philippine Demonstration.
Eligible beneficiaries for the Demonstration—TOP Standard beneficiaries, consisting of
retirees and their family members, TRICARE for Life, family members of active service
members, and TYA, Reservist, and National Guard who resided in the Philippines—
received care in the designated demonstration areas and used approved Demonstration
providers. Through this research I evaluated the following Demonstration areas: Metro
Manila and its surrounding areas of Cavite City, Cavite, and Iloilo City, Iloilo.
Interpretation of the Findings
The results of the study show that that men and women of all ages were similarly
satisfied with the health care finder functionality and ability to receive a waiver to receive
health care from a nonapproved Demonstration provider. However, these same
participants also felt that their out-of-pocket expenses were higher than before the
Demonstration.
According to Andersen et al. (2010) and Andersen and Newman (1973/2005), an
individual’s age and gender could play a role in the propensity for accessing health
services. However, when assessing the correlation of age and gender for the
Demonstration in Metro Manila, Cavite City, Cavite, and Iloilo City, Iloilo, there was

115
little evidence to suggest that Demonstration recipients had different opinions of health
care finder functionality or satisfaction requesting a waiver based on their age or gender.
Conversely, this indicated that men and women of all ages were similarly satisfied with
the health care finder functionality and ability to obtain a waiver to receive health care
from a nonapproved Demonstration provider.
The results also showed that participants were highly satisfied with the
Demonstration overall and were much more satisfied with their health care following the
implementation of the Philippine Demonstration. However, these same participants also
felt that their out-of-pocket expenses were higher than before the Demonstration.
Interestingly, an analysis of beneficiaries’ out-of-pocket costs for inpatient and outpatient
health care services for CYs 2011 and 2012 showed that beneficiaries’ out-of-pocket
costs were higher in the years before the Philippine Demonstration. After the
implementation of the Philippine Demonstration, beneficiaries’ out-of-pocket costs for
inpatient and outpatient health care services decreased for CYs 2013, 2014, and 2015.
Beneficiaries’ actual out-of-pocket costs based on inpatient and outpatient claims
data January 1, 2011, through December 31, 2015, showed a decrease in the amount
beneficiaries paid out-of-pocket in Metro Manila and its surrounding areas, Cavite City,
Cavite, and Iloilo City, Iloilo to providers not accepting TRICARE. Before the Philippine
Demonstration, the providers in the Philippines did not accept what TRICARE
reimbursed, which subjected beneficiaries to balance billing. Beneficiaries’ out-of-pocket
costs collectively were $147,320 (CY 2011) and $143,682 (CY 2012) for inpatient

116
services, shown in Table 8, and $368,029 (CY 2011) and $232,041 (CY 2012) for
outpatient services, shown in Table 11.
Schoen et al. (2010) argued that the design of the insurance plan influenced access
to medical care and costs. Upon implementation of the Philippine Demonstration, the
approved Demonstration providers agreed to accept the TRICARE reimbursement as
payment in full, eliminating balance billing for beneficiaries. After implementing the
Philippine Demonstration, beneficiaries’ out-of-pocket costs collectively were $65,529
(CY 2013), $172,507 (CY 2014), and $184,158 (CY 2015) for inpatient costs, as seen in
Table 9, and $91,521 (CY 2013), $157,590 (CY 2014), and $192,797 (CY 2015) for
outpatient costs, as seen in Table 12. Beneficiaries who chose not to receive care from
approved Demonstration providers’ out-of-pocket costs collectively were $74,695 (CY
2013), $51,312 (CY 2014), and $47,347 (CY 2015) for inpatient services, as depicted in
Table 10, and $96,412 (CY 2013), $39,848 (CY 2014), and $25,747 (CY 2015) for
outpatient services, as depicted in Table 13. Table 12 and Table 13 are rather revealing in
a few ways. These results are indicative that the beneficiaries’ out-of-pocket costs
actually decreased. Andersen and Newman (1973/2005) predicted that access to health
care would increase if the patient out-of-pocket expenses decreased. As the Philippine
Demonstration matured, more beneficiaries started accessing care from approved
Demonstration providers, indicating the efficacy and acceptability of a closed network
changing the health care model for delivering care and for reimbursement methodology.

117
Limitations of the Study
In reviewing the literature, there was no research found that integrated the MHS
with a foreign health care system to create an alternative for providing health care. This
research was limited to the patient experience. As previously mentioned, based on claims
data, out of approximately 10,000 TRICARE Standard beneficiaries living in the
Philippines, only 4,909 beneficiaries used the TOP Standard option before implementing
the Philippine Demonstration. The predisposing factors used to evaluate the Philippine
Demonstration were limited to age, gender, and location. The beneficiary categories were
collapsed so the TOP Standard categories or options could not be determined, rendering it
hard to decide which beneficiary category was receiving the most care. Additionally, it
was impossible to determine the number of beneficiaries accessing their TRICARE
benefit under the Philippine Demonstration as well as the beneficiary category.
Recommendations
Further research should be done to determine the full effects of the Philippine
Demonstration, evaluating the impact of predisposing factors for TOP Standard
beneficiaries accessing health care and trending actual health care expenditures paid by
the DoD, beneficiaries, and other health insurance. It should promote wellness programs
for TOP Standard beneficiaries that would result in better health outcomes. An approach
to the study from the perspective of the providers could also prove beneficial.
Implications for Positive Social Change
The TRICARE beneficiaries in the Philippines experienced a positive social
change at the individual level after effectively blending the MHS and the Philippines

118
health care system, which created a closed network, resulting in decreased out-of-pocket
costs and increased access to quality health care. The contractor responsible for
administering the Philippine Demonstration recruited providers who agreed to accept
what TRICARE reimbursed, which included the beneficiary’s deductible and cost share
as payment in full, alleviating balance billing. Furthermore, the providers agreed to
undergo a stringent credentialing process that assured providers provided quality health
care. This research has promising implications for the DoD and beneficiaries who live
and receive health care overseas. There is a high probability that health care expenditures
could decrease for the DoD and beneficiaries.
Positive social change for increasing access to quality health care and decreased
out-of-pocket costs can be accomplished when the DHA implements a closed network of
providers throughout various countries outside the continental United States, whereby
beneficiaries are not subjected to balance billing and have access to providers who
provide quality health care and accept what TRICARE reimburses as full payment.
Regardless of the balance billing law, the standards for health care, and access to
numerous providers in the United States, military retirees and their family members and
family members of active service members are subjected to higher out-of-pocket costs
and decreased access to quality health care in countries outside the United States.
Therefore, the DHA’s role in social change is to develop a strategy and legislation to
decrease out-of-pocket costs and increase access to quality health care for integrating the
MHS with foreign health care systems. Socializing this thought process will take time to
effectuate social change worldwide.

119
Conclusion
In conclusion, the results of the three RQs provide evidence of a positive
relationship between Demonstration recipients’ financial burdens and satisfaction with
the Demonstration as well as their confidence that their health care needs would be met
under the Philippine Demonstration. Although some beneficiaries believed that their out-
of-pocket costs increased, an actual analysis of the claims data showed a decrease in
beneficiaries’ out-of-pocket costs. Therefore, a closed network of approved
Demonstration providers proved to be beneficial for increasing access to quality health
care while decreasing beneficiary out-of-pocket costs.

