


Running head: THE TRENDS IN THE FINANCING OF US HOSPITAL CARE 1
The Trends in the Financing and Sources of Funds in the US Hospital Care
ASU-Tempe Campus
ECN 355 - Economics of Health Care
November 22, 2019

THE TRENDS IN THE FINANCING OF US HOSPITAL CARE 2
Abstract
This study is an analysis of the patterns in the financing of hospital care in the United States and
the variations in the means of funding for the same matter throughout the years. Hospital care is
still the biggest single item in the U.S. healthcare system, where it takes almost one-third of the
total healthcare expenditures by 2018. The research with a quantitative approach mainly based
on secondary data from sources like the Kaiser Family Foundation and government health
expenditure reports has drawn a map of increase in hospital spending from the 1970s to
currently. Results show hospital expenditures have been going beyond general economic growth
every time, which has been largely caused by the mentioned factors, demographic changes, the
rising number of people with chronic diseases, new technology, and increasing wages and
operational costs. Besides, the report describes dramatic changes in the structure of the
financing: in the past, out-of-pocket payments were the main source of financing, but
considerable federal programs such as Medicare and Medicaid, private insurance, philanthropy,
and the introduction of public-private partnerships have contributed to a more varied hospital
funding landscape. Although there is a spread in the sources of hospital funding, the federal
government still holds the pole position as the main source of hospital financing. The study in
the end declares that the US hospital expenses will rise and the need for the more sophisticated
treatment will be the main reason for the growth. Thus the necessity of a money system that is
capable of adjusting to the change and implementing sustainable policies to guarantee both
accessibility, efficiency, and system stability in the long run.

THE TRENDS IN THE FINANCING OF US HOSPITAL CARE 3
Introduction and background information
The largest sector in the health care system in the United States is hospital care. These
hospitals serve the health care needs of the majority of the population in the country and require
immense funding to cater for these services. Cleverley and Cleverley (2017) say that the sources
of funding for these hospitals range from a number of sources which include both public and
private funding. There are also those ones that are nonprofit in nature and most of them are
funded by donations from their donors and they also receive endowments. Over the years,
however, these funding sources have changed. The amount of funding and the sources have
become dynamic which has made the hospitals dynamic in its service delivery as well.
In the 1980s, the hospital spending in the United States was merely about $600 million
which by the end of the 1980s has risen up by about 14%. By the end of 2018, the spending on
hospital care in the country had risen to $3.7 trillion, a whopping percentage increase since the
1980s. When compared to 2017, the 2018 expenditure shows a 5.3% increase (Kaiser Family
Foundation, 2019). It also shows that hospital spending in the country, over the decades, has
grown more than any other sectors of the economy. This trend translates to an upward trend in
hospital care funding in the country. Some of the major sources of these finances to this sector
include the traditional sources such as community donations and grants, long-term debts and
bonds. Other major sources include employer-based health insurance, private insurance
coverage, out-of-pocket spending and cost sharing, safety nets and the federal government.
The transitions of the U.S. hospital system funding models have also deeply influenced
financial planning, priority allocation, and long-term sustainability endeavors. In their paper,
Keehan et al. (2015) pinpoint that projections for the national health expenditures not only mirror
the economic growth cycle but also the changes in policy and the impact of the demographic

THE TRENDS IN THE FINANCING OF US HOSPITAL CARE 4
factors like the aging of the population. This means the hospitals have to be prepared for the
demographic changes and the policy adjustments in the future if they want to remain financially
stable. This has led hospitals to creating other sources of income to complement the revenue
from grants and subsidies. Kaiser (2019) is of the view that hospital revenue covers the
increasing proportion that is dependent on insurance reimbursements and federal programs,
especially the competition between private payers is becoming more intense. Therefore, hospitals
are vulnerable when changes in insurance happen or when the government sets new policies.
Cleverley and Cleverley (2017) reveal that hospitals are coming up with strategies for financial
management which are aimed at stabilizing the operating margins in the case of changes in the
sources of funds. The same they do are among the indicators of the importance of good financial
governance to hospital performance, on a par with clinical effectiveness. Additionally, such
changes have led many providers to consider their capital investments, renegotiate payer
contracts, and adopt various cost-efficiency measures to continue operating during periods of
revenue unpredictability,
One more significant trend which largely impacts hospital funding is the advent of the
practice of linking the performance and the amount of money a hospital gets from the budget
based on this performance. According to Kaiser (2019), the relationship between health care
spending and the US economic output puts a heavy burden on policy makers to link hospital
funding to outcomes that can be quantified. This means hospitals have to show efficiency and
honesty in the way they utilize resources. Burill (2018) observes that with the changes in
payment models, the criteria on which hospitals are judged are being adjusted and consequently
hospitals will be assessed through patient satisfaction, quality, and readmission rates. This trend
demonstrates a closer hospital reputation and funding relationship with patient-centered

THE TRENDS IN THE FINANCING OF US HOSPITAL CARE 5
performance. According to Kaiser Family Foundation (2019), hospitals relying on Medicare and
Medicaid funding are subject to the strictest reporting requirements which they must meet in
order they can maintain their levels of reimbursement. The picture is that regulations are the
enforcers of accountability while at the same time they determine the financial outcomes. First of
all, they need to understand that there are incentives which are making them go in the direction
of cutting down on costs, simplifying, and then also becoming more efficient which is exactly
what they do. The article by Keehan et al. (2015) shows that there are changes in the hospital
industry which have led the latter to adopt cost-cutting practices, reduce administrative overhead,
and enhance their efficiency. So, in their opinion, quite an innovative approach to the institution's
everyday activities is not an option anymore, it is absolutely necessary. Cleverley and Cleverley
(2017) give their opinion that in the present day a hospital can maintain its financial health only
when it manages to satisfy the requirements of the regulator and at the same time remain
operationally flexible which is especially the case when hospitals have to deal with the
increasing volume of patients and the growing demand for staff caused by the competition for
funding. This shows us the hospital that is capable financially to adjust is the one that has the
resilience of the organization at its core.
Methodology
The research method used in this research is a quantitative research method. This method
was used to explore the topic of hospital financing trends in the United States. Through this
method, the researcher was able to gather data from the spending explorer and other secondary
sources had crucial data concerning the trends in financing and the sources of finances for
hospitals in the country. Therefore, the data collection was primarily based on already existing
data from the explorer and credible websites on health care. In doing this, the researcher was able

THE TRENDS IN THE FINANCING OF US HOSPITAL CARE 6
to collect reliable and accurate information and data on the topic. It was analyzed and presented
in graphs and charts. The method was also quick and cheaper since it did not require going to the
field to collect primary data.
Besides that, the study mostly depended upon existing data. It also implemented a more
formal structure in the selection of the sources so as to ensure that the sources used are not only
reliable and relevant to the research question. Information from such data repositories as Kaiser
Family Foundation (2019), and analyses by Cleverley and Cleverley (2017) have been chosen for
the reason that they provide a variety of financial considerations of the hospital expenditure
patterns across the federal, private, and the non-profit sectors. These secondary sources were
weighted to support the objectivity of the research and to reduce the interpretive bias, which is a
frequent problem in primary data collection. Keehan et al. (2015) came up with money-related
projections over a certain period which facilitated the study’s resource tracking ability. The
researcher, by that method, was able to follow the development of the money spent in several
branches over the last 20 years or more without encountering the problems related to conducting
surveys or interviews. As most of the data had already been checked and published after going
through peer review, the process of triangulation was more convenient and trustworthy. This
multilayered sourcing strategy increased the extent to which findings are true while still being
efficient in terms of quantitative secondary research cost.
Comparative and descriptive statistical methods were implemented in the analysis to
enhance the consistency of the data. Besides these methods, the visual interpretation instruments,
for instance, a graph and charts also attracted an essential part. As Kaiser (2019) states, the
graphical representation is most vibrant, among other things, to display the increment in
expenditures relative to the GDP trend over time. The researcher, availing of the data by the

THE TRENDS IN THE FINANCING OF US HOSPITAL CARE 7
Kaiser Family Foundation (2019), turned the raw numbers into the pictures of the trends which
later on made the comparison of the different funding sources such as government programs,
insurance and community-based contributions easier. Cleverley and Cleverley (2017) assert that
while numbers are used, the understanding of changes in the distribution of the financial
resources among various organizations, becomes much simpler. This type of results’
organization enabled the researchers to accomplish the task of both upholding the data’s
numerical accuracy and rendering the findings in a more user-friendly way to the non-technical
audience. Keehan et al. (2015) maintain that incorporating graphical representation of the trends
in their study of hospital financing is a way to envisage future financing needs. This method of
analysis allowed the research to not only recount the existing facts but also to recognize the
patterns and potential ramifications related to changes in the funding structure and priority of
expenditures.
Research Findings
Hospital care financing has increased over the years
Over the years, remarkable trends have been observed in spending and financing in
hospital care in America. The total expenditure in the country since the 1970s shows an upward
increase in spending which means hospitals spend more money than before. In the 1970s for
instance, the expenditure was mere $500 million. However, over the years, it has substantially
increased to a billion dollars. As of 2017, the total health expenditure in the country was at $3.5
billion. What is more serious about this trend is that it has grown to a point that it has outpaced
the national economic growth (Kaiser Family Foundation, 2019). This trend is also backed up by
the national allocation of funds to the hospital acre in the country. In the 1970s, it was at 6.9% of
the entire GPD. This is no longer the case because in 2017, the allocated funds for this category
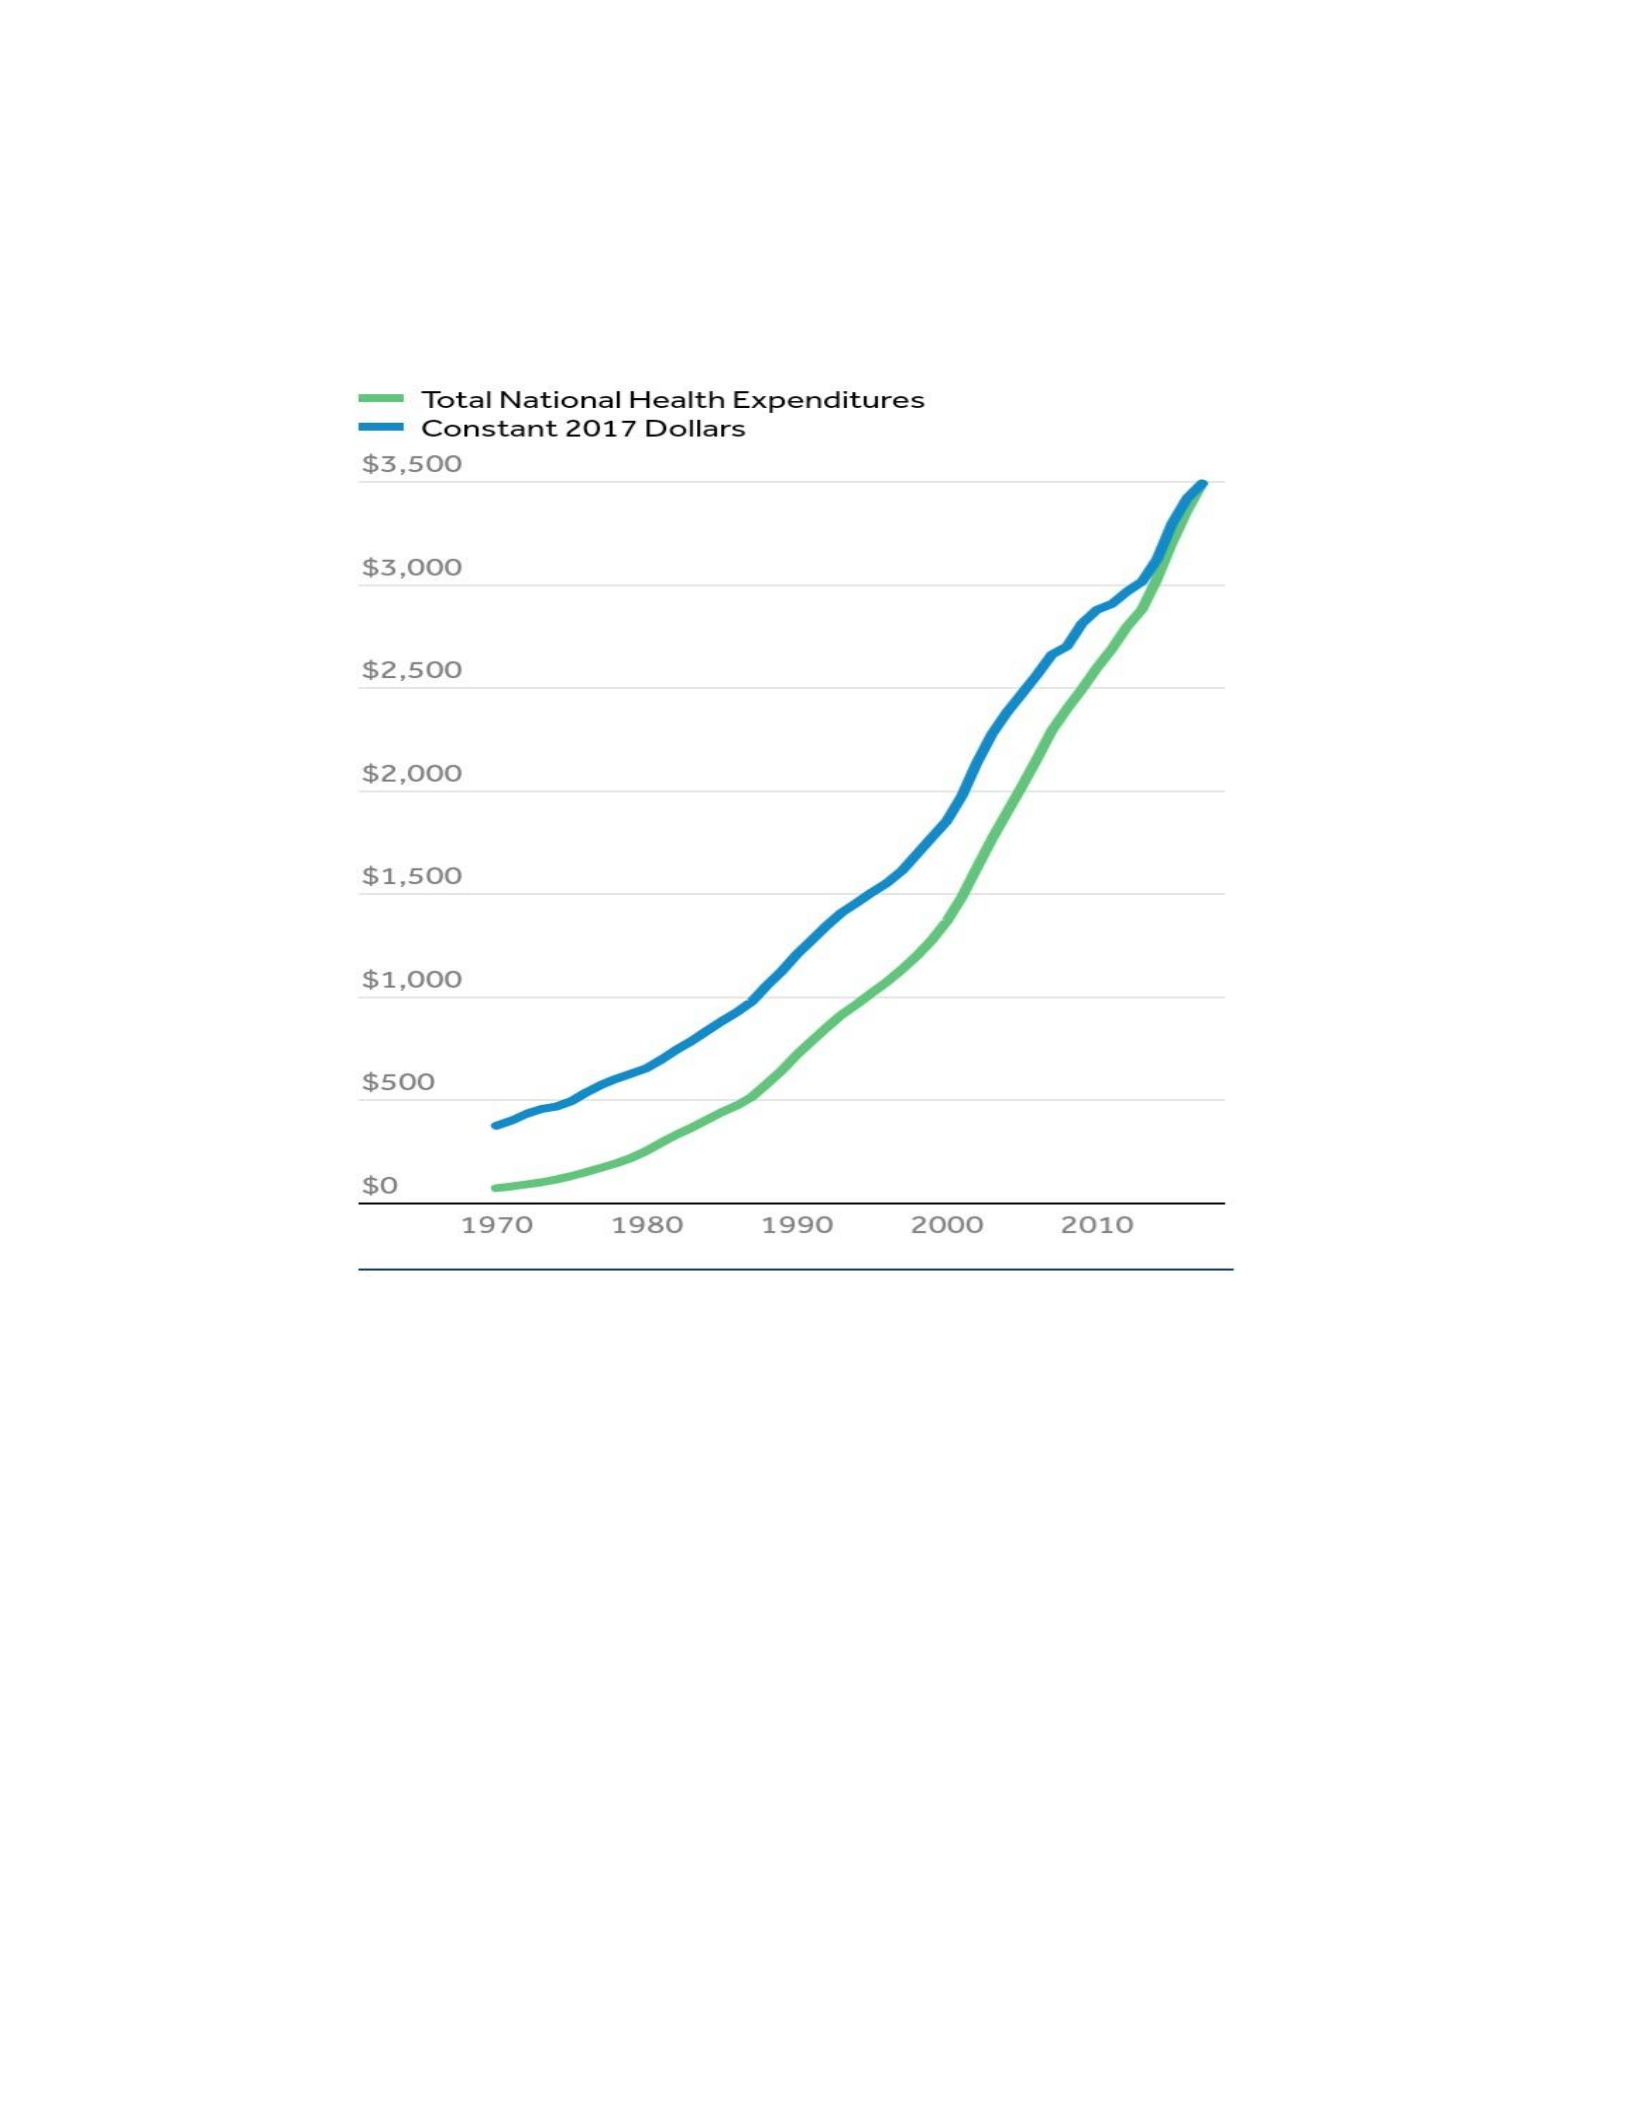
THE TRENDS IN THE FINANCING OF US HOSPITAL CARE 8
was 17.9%. The figure below illustrates the trends in the financing of healthcare in the USA from
the 1970s to 2017.
Figure 1: The figure illustrates the trends in the financing of healthcare in the USA from the
1970s to 2017.
Source: Kaiser Family Foundation Analysis of National Hospital Health Expenditure.
Chronic disease management has been identified as the main reason for the escalation of
hospital costs in the United States, and it is claimed that more than half of the increased hospital
costs are due to this issue. Hospitals have to double their resources both to supply the emergency
requirements and to undertake the long-term treatment since patients with diseases like diabetes,

THE TRENDS IN THE FINANCING OF US HOSPITAL CARE 9
cardiac problems, and cancer keep living longer with their ailments. In an article by K. Carrera,
H. Kantarjian, and V. Blinder (2018), the authors explain that the financial toxicity of cancer
care is a reflection of the overall trend of the increasing costs of specialized treatment. Indeed,
most of the times that developments in medical care are proclaimed, new financial hurdles
accompany them. The hikes are not only related to drug pricing, rather these also include
hospital stays, the use of advanced diagnostic tools, and follow-up services. Besides that,
Zimlichman et al. (2013) demonstrate that healthcare-associated infections result in unnecessary
economic burdens that cause a significant increase in expenditures. Their research points to the
fact that the complications, which can be avoided, may become sources of hidden financial
burdens on hospital budgets. Zimlichman et al. (2013) say such expenses can become obsolete
very quickly, especially extended hospitalization or readmission for the recovery process. Curtis
(2013) mentions that unit costs for medical services and personnel have also been rising
constantly over the years, which has contributed to the increase of hospital expenditures more
than the inflation rate. The implication is that even everyday services now require higher
operating budgets than those during the previous decades. Collectively, these factors say that the
shifts in disease patterns, coupled with the technological and service-based price increases, have
been the major drivers of the hospital financing surge over the years.
The hospital financing has been accelerated by economic instability and market
fluctuations just as much as by other factors. The scenario during economic recession, whether
national or global, is that the health systems will suffer from cuts to their budgets, lower
donations, and less government subsidies. Karanikolos et al. (2013) provide that austerity
measures in various countries which were introduced after the financial crises have led to sums
of health budgets being squeezed and services being slowed down. It tells how government

THE TRENDS IN THE FINANCING OF US HOSPITAL CARE 10
changes in priorities may cause funding structures to be fragile very fast. The situation in Europe
described in this research is similar to what has already happened with American hospitals
wherever there have been economic problems. The fiscal flexibility in the U.S. has been reduced
turning hospitals into the place where operational costs keep rising. Mills (2014) reports that
hospitals in low- and middle-income areas become more fragile if financial shocks take place, so
it follows that even strong economies do not guarantee stable health financing. His statement
underscores that the support of institutional resilience depends on the existence of a plan, rather
than on the wealth of a nation alone. Moreover, Curtis (2013) finds out that when government
reimbursements are below real costs, hospitals are left with no option but to make up the
difference through debt, insurance negotiation, or billing adjustments. These changes can cause
additional long-term repayment burdens on the healthcare system, thus further exacerbating the
issue of systemic expenditure. This process over time leads to an increase in the volume of
capital that is necessary for the continuation of the operations which is what calls for the upward
trend in health financing to be re-enforced again and again.
Technological innovation, nonetheless that patient outcomes have been positively
affected by, has increased the financial demands in hospitals. The use of advanced diagnostic
equipment, digitized records, and robotic surgery has to be accompanied by hefty capital
investments made on the equipment plus the constant maintenance and training. According to
Yip et al. (2012), even amidst China's reform initiatives, hospital technologies complicated the
situation by leading to a substantial rise in health expenditure. This situation throws a light on the
fact that modernization of healthcare always comes with financial trade-offs. Similar trends have
also been discovered in the healthcare system of the United States when hospitals are trying to
level the playing field by adopting the new standards of higher care. Carrera et al. (2018) state

THE TRENDS IN THE FINANCING OF US HOSPITAL CARE 11
that technologies form the basis of the only source of the most expensive treatments in
oncological and other specialized fields. In their opinion, the advancement in high technology is
the main reason for the increase of the healthcare budget in both inpatient and outpatient settings.
Moreover, Zimlichman et al. (2013) reveal that infection prevention technologies are among the
causes of increased short-term costs although the patient complicacies are minimized. Thus, it
can be inferred that cost benefits may not be immediate even when the interventions are effective
in nature. Curtis (2013) also points out that the higher the level of technology, the greater the
need for highly skilled personnel and thus the cost involved in recruiting the right personnel will
escalate the hospital sum operation. In effect, these are long-term operational costs that
contribute to the hospital financing needs besides the initial investment. Many of these expenses
have been recurrent to the extent that the hospital has had to resort to different methods in
financing such as the use of hospital bonds, the sale of collections, fees and loans, among others.
Over time, hospitals have utilized different financing methods such as the use of hospital bonds,
the sale of collections, fees and loans, among others. This has been necessitated by the recurrent
expenses that have impacted the hospital's finances.
Across the United States, changes to the demographics have additionally caused an
increased demand for hospital funding. The need for inpatient services, specialized procedures,
and long-term care, escalates significantly as populations age. Mills (2014) clarifies that aging
populations in varied health systems result in higher levels of per capita spending, particularly
when chronic conditions are common. This correlation brings out the direct association between
age-related illness and cost escalation. Karanikolos et al. (2013) also point out that financial
shocks may have different effects on healthcare depending on demographic profiles, hence, older
populations might be the ones requiring more stable expenditures. Consequently, the structure of

THE TRENDS IN THE FINANCING OF US HOSPITAL CARE 12
the population can determine the rate of costs being accumulated. Infections risks tend to get
higher with age and hospital exposure, thus, adding to the problems of the vulnerable groups, as
stated by Zimlichman et al. (2013). Their research shows that clinical vulnerabilities become
financial liabilities. Curtis (2013) goes on to say that the unit costs of specialized geriatric care
have increased over time due to the needs of the workforce, training, and equipment. In other
words, the distribution of resources must change to correspond with the new patient needs. These
demographic trends are contributing factors to existing inflationary pressures which together
signify the long-term increase in financing requirements, thus, illustrating that hospitals cannot
rely on previous funding models to meet the current demand.
A different element that leads to the increase in the financing of the hospital is the
continuous increase in the costs of labor, administration, and operations. Curtis (2013) points out
that the wages of the medical professionals, the support staff, and the administrative personnel
have been going up, especially as the hospitals are competing for the specialized talents. The
trend is indicative that just the human resource needs are a major contributor to the expansion of
the budget. Moreover, Yip et al. (2012) outline the mechanism of restructuring and reform in
large health systems by which they are usually incurring transitional expenses that lead to higher
overall costs. The several changes in the short term can initiate a series of financial adjustments
which is a longer period. Karanikolos et al. (2013) emphasize that austerity measures, instead of
cutting down on long-term spending, may necessitate short-term investments to keep the levels
of staffing and the infrastructures high. Their position is indicative of how the cutting of costs
can paradoxically cause the rise of expenditure. Besides that, Zimlichman et al. (2013) illustrate
that the administration of the hospital-acquired infections constitutes additional financial burdens
specifically in cases when new personnel and monitoring systems are required. In this way,

THE TRENDS IN THE FINANCING OF US HOSPITAL CARE 13
operational risks become financial losses. The aggregate of the labor and operational
requirements for hospitals has been a major factor in the steady increase in their expenditure that
has, to a great extent, surpassed other sectors of the economy. It is evident that hospital financing
growth is not a matter of isolated spending trends but multiple intertwined factors.
International comparisons also elucidate the reason why hospital expenditure in the
United States is perpetually rising. Yip et al. (2012) portray that China`s swift reform initiatives
required a big outlay to refurbish the facilities, train personnel, and set up insurance mechanisms.
This instance indicates that progress is normally accompanied by a financial crisis. Although the
context is different, the core idea of modernization leading to rising costs is still applicable in
different countries. Mills (2014) underlines that in poor and middle-income countries, the
increase of health expenditure is usually in line with the commitment to broaden coverage or to
introduce new technology. This is congruent with the global pattern of increased spending as
systems modernize. Zimlichman et al. (2013) convey that infections may cause a financial
burden not only in the United States but also other countries, pointing out that global health
systems share these cost challenges. Their results indicate the inevitability of expense in the
absence of prevention. According to Carrera et al. (2018), the cost of cancer treatment all over
the world is going up and that in several regions it is becoming one of the reasons that constrain
hospital budgets. In other words, the trend of specialty care turning into a financial burden
irrespective of location continues. The dependence on private insurance in the U.S. system,
together with the focus on leading-edge care delivery, escalates the size and speed of the
financing requirements that are necessary to compare with the countries having centralized
funding structures.
The emergence of new sources of funds

THE TRENDS IN THE FINANCING OF US HOSPITAL CARE 14
The other observation made in this research is that the sources of funds have changed
over the years. For instance, Keehan, et al., (2015) states that there have been major shifts since
the 1960s in the way hospitals are funded because Medicaid and Medicare did not exist. Over
half of the hospitals in the country were only covered by insurance funds. What this means is that
the other funds came from the other patchwork of a variety of sources both public and private.
During these years, the majority of the paid hospital bills from their pocket. However, a dramatic
rise in the private insurance sector changed the situation. Consequently, by 2016, the payment
out-pockets of the patients reduced over 16%.
Additionally, other sources of hospital funding have emerged that covers other crucial
matters such as the financing of facilities. Some of them include the federal housing
administrative funds that fund the building of facilities (Kaiser, 2019). Other include the
emergence of nonprofit and for-profit funding. Partnerships have allowed most of the non-profit
hospitals to raise capital for its services, an aspect which did not exist many decades ago. The
other growing trend in this regard is the private equity investment, a method of funding hospitals
in the country especially for those most fiscally unstable ones.
The significant changes that took place in the financing of hospitals is the expanded role
of the federal government in facilitating a wider coverage of insurance and the affordability of
the care. In his book, Obama (2016) mentioned that the Affordable Care Act implementation had
significant effects on various fronts among the major ones being improvements made to the
insurance market places, lowering the number of the uninsured and extending the eligibility of
Medicaid. It can be seen from this that changes made at the level of the national policy can result
in a direct influence of the cash inflows of hospitals. The National Center for Health Statistics
(2012) also noted that no-funds programs are more important than in past decades for patient

THE TRENDS IN THE FINANCING OF US HOSPITAL CARE 15
coverage, indicating a change from care funded by individuals to structured financing systems
driven by policies. In other words, public financing trends over the years have been replacing the
older models of personal payment and limited insurance coverage. Zimlichman et al. (2013)
mentioned that the economic consequences of avoidable hospital complications could be one of
the reasons for a more active policy role since cutting down on complications is one way to
directly help both government payers and hospital budgets. What they basically mean is that the
financial resources saved as a result of the incorporation of preventive strategies into the general
funding frameworks become one of the attractions of these combined efforts which represent the
expansion of the funding channels based on policy that complement the traditional sources of
insurance.
Along with the mentioned, data-driven decision-making and performance-linked
incentives based on the observable patient outcomes signify a new area of financial support. A
study by Sherman et al. (2016) illustrates how payers are using real-world evidence to decide
value and to allocate resources in a more efficient manner. This is a clear indication that there
has been a major change in the way data collection and interpretation are recognized in
reimbursement planning (Calvert et al., 2013). The patient-reported outcomes are the dominant
factors now when negotiating reimbursement with funding levels being linked to quality-of-care
metrics. The essence is that hospital systems have to modify their reporting in order to qualify
these new routes of financing. Obama (2016) equally pointed out that hospitals with good
performance and low readmission rates can more easily access the incentive-based funding. It is
noted that healthcare models that reward efficiency and measurable improvements in care quality
are becoming more popular gradually. According to Zimlichman et al. (2013), these practices are
opening the way for funding that depends on openness, clinical effectiveness, and outcome

THE TRENDS IN THE FINANCING OF US HOSPITAL CARE 16
documentation, thus transitioning from the traditional fee-for-service models and allowing for
financing reforms that are sustainable.
Philanthropy and mission-driven funding sources have also changed to address needs that
go beyond expenses related to operations. According to the National Center for Health Statistics
(2012), donations from charities and donor-funded programs were traditionally directed towards
community benefit initiatives and indigent care. This shows that philanthropy was once mainly
used as a safety net rather than a development tool. Nevertheless, hospital endowments have in
recent years progressively contributed to the development of research collaborations, setting up
of specialized treatment centers, and also infrastructure upgrading. Tacconelli et al. (2018)
observed that donors' mindset has moved from global worries like antibiotic resistance to
funding directly research and innovation through hospital-affiliated programs. Hence,
philanthropic support can follow health emergencies all over the world almost immediately.
Zimlichman et al. (2013) further say that funds from outside sources directed towards infection
prevention can be a solution to the raising of costs, lessening of financial burden on the long run
and giving financial relief to the facilities. Their argument illustrates that harm prevention could
be a clever way to reach the necessary resources that are targeted. These changes represent a
more significant shift in the charitable focus, which is no longer solely based on humanitarian
relief but rather on the strategic investment that is aimed at hospital competitiveness and
innovation capacity.
Private-sector collaboration has been more popular as hospitals look for cash through
partnerships that are not usual. Obama (2016) said that public-private models could be the link
that fills the financial gap left by government programs. Therefore it indicates that hospitals are
realizing that they might need a combination of financing strategies to stay afloat. On the other

THE TRENDS IN THE FINANCING OF US HOSPITAL CARE 17
hand, Calvert et al. (2013) point out that performance tracking and data openness are the factors
that make these kinds of partnerships more profitable because the investors are looking for a
return of an investment that is quantified. Agreeing with the authors’ viewpoint, accurate
measure-able objectives allow external partners to feel more confident about the allocation of the
funds. According to Tacconelli et al. (2018), the findings of research-intensive collaborations
between the pharmaceutical industry and hospital systems have fueled for drug development,
novel infectious disease control strategies, and clinical trials were few. These facts illustrate that
innovation incentives play more significant roles in drawing private capital. Sherman et al.
(2016) add that real-world data projects can become another point of joint investors' interest,
especially in cases when hospitals show the possibility of evidence collection and
implementation of efficient insights. Their position reflects that the data capabilities can act as a
factor for further collaboration. These growing partnerships, which are beyond usual bonds and
loans, are playing a part in stabilizing hospital finances while at the same time encouraging
innovation and strategic growth.
Hospital care takes the largest share of the health care funding
The other finding is the hospital sector in the United States of American consumes more
funds allocated from the various sources. Kaiser Family Foundation. (2019) asserts that it is
estimated the hospital care covers of 33% of the entire funds allotted to the health care system in
the country by the end of 2017. Interestingly, research from this study also showed that of all the
sources of these funds that go to the hospitals, federal government funding remains the leading
lender providing over 45% of the funds followed by the insurance funds. In 2018, for instance,
the US federal government allocated about $1.1 trillion to the sector. The figure below illustrates
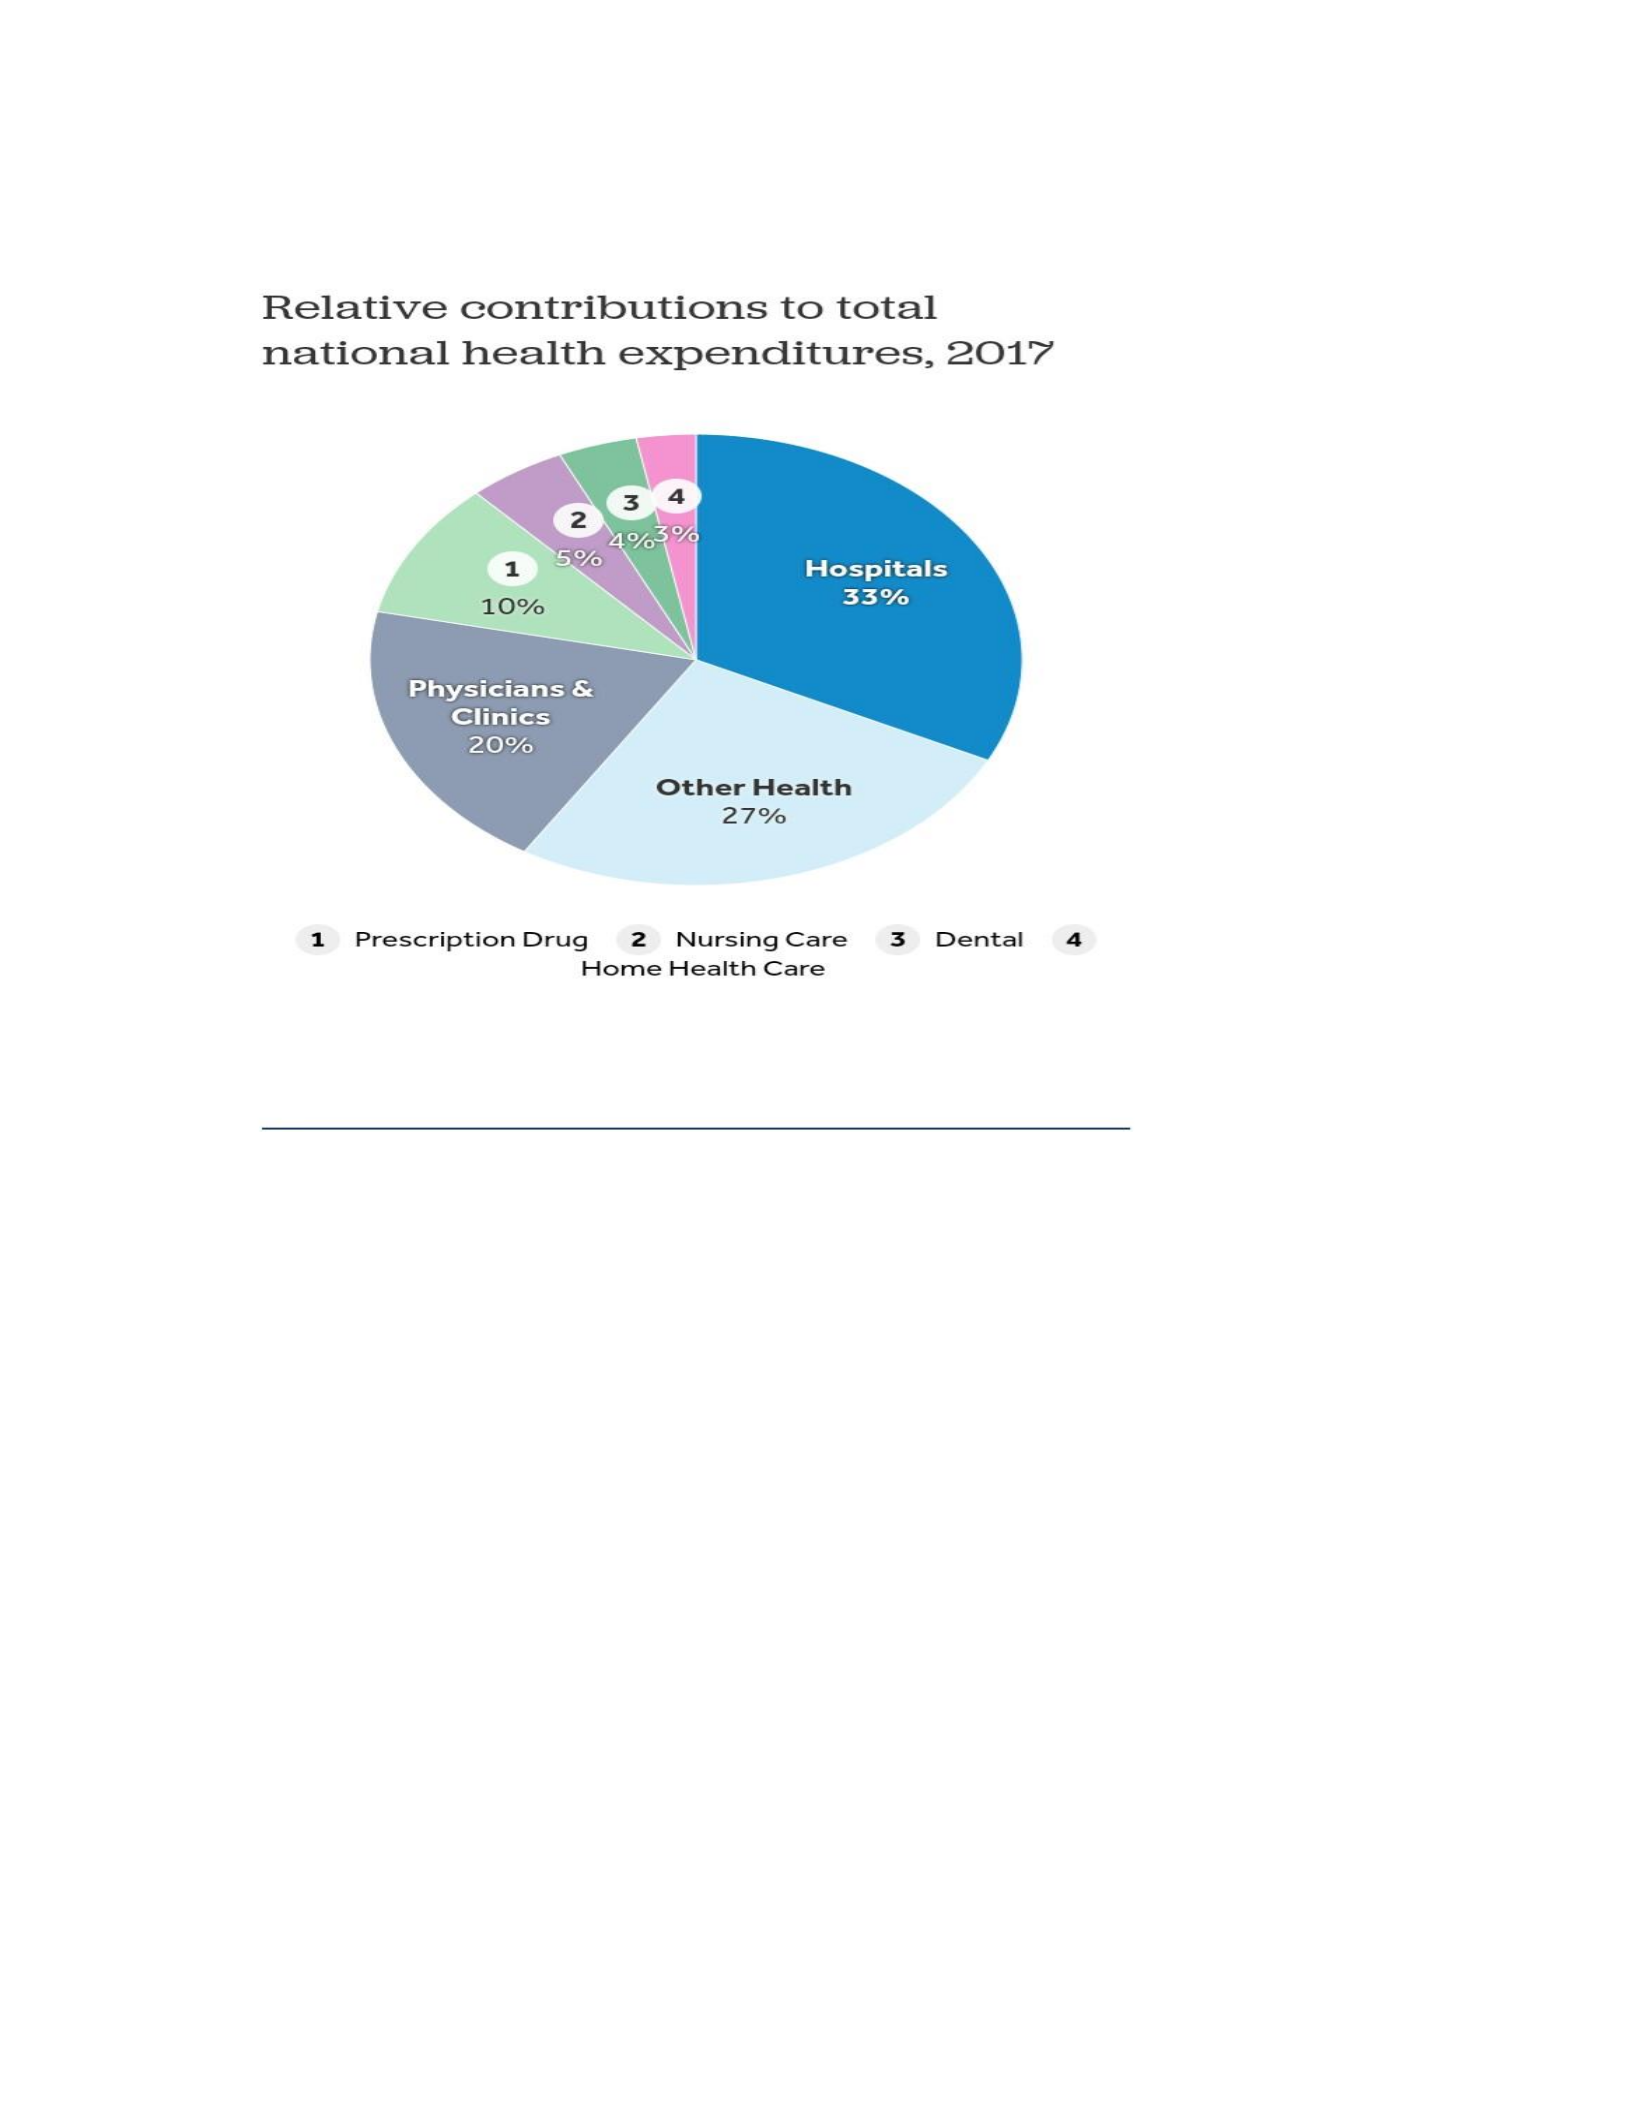
THE TRENDS IN THE FINANCING OF US HOSPITAL CARE 18
the hospital care share of healthcare funding (Burill, 2018).
Figure 2: Illustrates the hospital care share of healthcare funding.
Source: Kaiser Family Foundation Analysis of National Hospital Health Expenditure.
One of the reasons that hospital care takes up the biggest part of the national health
expenditure is that hospitals have to provide a wide variety of services, most of which are costly.
In their article, Moses et al (2013) point out that hospitals not only offer emergency care but also
give advanced surgical treatments, provide intensive care, and conduct specialized diagnostics
that require a lot of infrastructure and technology. Consequently, hospital services by their nature
entail higher spending in multiple areas. Most of these services are, therefore, 24-hour services,
which means that staffing and maintenance will be on a higher level than usual. Dieleman et al.

THE TRENDS IN THE FINANCING OF US HOSPITAL CARE 19
(2016) indicate that hospital care is the main cause of high labor costs, as the number of medical
staff which include physicians, nurses, technicians, and administrative personnel who are needed
to perform the given treatment, is high. Hence the workforce element alone accounts for a very
big part of the total operating budgets. Besides that, Papanicolas, Woskie and Jha (2018) remark
that the United States is more inclined to hospital-based care than other high-income countries
and this is the reason why the hospital sector takes a larger share of the total healthcare
resources. This comparison brings out the differences in the structures of national systems in
how they allocate funds. All these factors collectively help us understand why hospitals are still
the single biggest cost center in the financing landscape.
The nature of the healthcare market in the U.S. is such that it continually imparts the idea
that hospital financing is the major contributor to both public and private spending. Cutler and
Morton (2013) are of the opinion that mergers between hospitals have resulted in the increased
influence of those institutions on the market, thus allowing them to have higher prices set when
they deal with the insurers. Consequently, this formula makes it possible for hospitals to be on
the same contractual terms where the balance of power in the market is their increasing role.
Such a situation almost always implies that more favorable reimbursement estimations for
inpatient and outpatient services are obtained from hospital-owned settings. Papanicolas,
Woskie, and Jha (2018) add that prices for medical procedures in the U.S. are much higher than
in other affluent nations. The authors thereby imply that bargaining over payments and the
market concentration have a major impact. The difference from peer countries illustrates how
pricing norms at the systemic level affect spending patterns. Dieleman et al. (2016) demonstrate
that growth in the number and the complexity of hospital cases further magnifies the hospital
share of healthcare funding since more complex cases cause higher per-patient costs. Thus, the

THE TRENDS IN THE FINANCING OF US HOSPITAL CARE 20
trend actually ties expenditure increase to the escalation of the severity of cases and the demand
for treatment. Such a situation has led to the hospital environment where hospital care is still the
main recipient of financial resources though in an unbalanced proportion.
In addition, the hospitals are responsible for handling some major public health issues
apart from the direct treatment of patients. Moses et al. (2013) clarify that in many cases
hospitals deliver a lot of uncompensated care to uninsured patients without any charge, thus
subsidies from government programs and cost-shifting to the insured population are what makes
it possible for these services to be provided. This system guarantees access but at the same time
there is a financial load on the institutions. Dieleman et al. (2016) report that public health
funding and emergency preparedness activities are the sources of hospital infrastructure which
supports hospitals’ role as the easiest safety-net providers. This reliance is a confirmation of
hospitals being at the center of crisis response and community health planning. Househ (2013)
points out that the use of digital platforms and telehealth systems by hospitals has made it
possible for them to extend their services and also effectively manage communication with
patients which has translated into more financial commitments to meet technology upgrade
requirements. This move is in line with the general trend of hospital engagement and virtual care
provision. The increase in these responsibilities has led to a hike in operating costs and it is
therefore necessary that higher funding allocations are made to enable the hospitals to remain
functional and to comply with public health directives.
One among the factors is the United States regulatory environment that leads to hospitals
getting excessive funding shares. Papanicolas, Woskie, and Jha (2018) stated that meeting
accreditation standards, safety requirements, and quality reporting systems requires a 'big
administrative investment'. This leads to the addition of various layers of 'oversight' that have

THE TRENDS IN THE FINANCING OF US HOSPITAL CARE 21
their own staff and facilities. Cutler and Morton (2013) claim that the hospital systems' mergers
and acquisition processes propel the legal, financial, and regulatory spending that results in
higher indirect costs of service delivery. Typically, the mentioned activities see the recruitment
of external advisors, lawyers, and managers for the integration of the system. According to
Moses et al. (2013), the process of performance metric reporting is very time-consuming, and
only a few specialized departments can do it. As a result, the accountability in the hospital has
made the collection and analysis of data its main tools. Househ (2013) says although these rules
are aimed at raising the quality and the accountability, they still lead to higher costs in operating
under the federal and state regulations, which, in turn, allows hospitals to get a bigger slice of the
health care system resources over time.
Hospitals are being burdened by the rising costs resulting from the demographic changes
and population health trends. According to Dieleman et al. (2016), most of the health problems
of the elderly are chronic in nature and they require inpatient interventions. Consequently
hospitals infrastructure and staffs are in a steady demand as the care needed is long term and
usually exceeds the capacity of outpatient services. Moses et al. (2013) emphasize that hospitals,
in particular, the referral centers, are the ones taking over the complicated cases and this results
in the concentration of expensive treatments in fewer institutions. This, in turn, makes these
major facilities that have specialized capabilities and advanced technologies continue to need the
upgrading of equipment that has to be continually done. Papanicolas, Woskie, and Jha (2018)
also give as a reason for hospital expenses the increasing hospital use, for example, hospital
emergency visits that occur frequently. This development is indicative of a more extensive
underlying systemic dependence on hospital-based care as a safety net, particularly prevailing in
areas with poor access to primary care. Besides, there is a condition that impacts the financial

THE TRENDS IN THE FINANCING OF US HOSPITAL CARE 22
situation of many hospitals, which is the situation when they have to deal with care that is either
completely unpaid or is underfunded, thus, their budgets are stretched even further. These
demographic and epidemiological changes have turned hospitals into the major players of
national care programs, which means a higher percentage of the available funding is allocated to
this sector every year posting further challenges of selecting the areas for spending that are the
least affected.
Patient expectations combined with changing care models are pushing hospitals to rely
more on their facilities for financial stability. Househ (2013) reports that digital communication
platforms deployed in hospitals enable patient engagement and remote monitoring; however,
they do still require IT infrastructure and security investments. These modifications have a
recurring nature of expenditure which goes beyond the very first installation. Some of the
expenses included are system maintenance, software updates, and the salaries of the specialized
IT personnel. According to Cutler and Morton (2013), the consolidation of hospitals results in
the extension of the service scope, thus enabling the provision of complete care pathways that
come with integrated administrative costs by the institutions. Even if this concerted effort can
result in the services becoming more efficient, the sum of overhead will still be more because
larger systems will still have to coordinate departments, standardize protocols and, ensure
compliance across multiple sites. In addition, Moses et al. (2013) say that the hospital is the main
responsible body for clinical research, training, and innovation initiatives that, however, require
the reinvestment of finances. These endeavors contribute to the institution's prestige; however, it
is necessary to firstly have the funding, good grant management, and partnership with the
regulatory bodies. On top of that, people's yearning for cutting-edge therapies and instant
accessibility to medical data is yet another factor fueling the pressure in hospitals to obtain the

THE TRENDS IN THE FINANCING OF US HOSPITAL CARE 23
necessary technology and human resources in order to face the challenge. The modifications of
this kind make hospitals more prominent players in the health ecosystem and, therefore, they
receive the biggest share of funding as they position themselves as care and system-wide
advancement hubs.
The Emergence of New Sources of Funds
One of the most remarkable phenomena leading to new financing in U.S. hospitals is the
massive expansion of federal health programs such as Medicare and Medicaid. The original
article points out, among other things, that these funds appeared after the 60s, but it does not give
any detailed information about their financial impact. According to Marmor (2017), it was just as
much a political process as an administrative one through which the evolution of Medicare had
occurred, with various reimbursement models being put to practice depending on demographic
pressures, hospital lobbying, and federal regulatory changes. According to Ventola (2015), over
the years, Medicare has broadened its scope from eldercare to supporting teaching hospitals and
critical access facilities, thereby ensuring financial stability in remote areas and allowing the
continued infusion of specialized services and infrastructure improvements. The same goes for
Medicaid, which has turned safety-net hospitals into places where low-income patients can be
treated without the hospitals having to suffer the uncompensated costs entirely, thus, those
institutions can both continue their operations and work with the health disparities in the
surrounding communities. These changes show that government funding is not exclusively
additive; on the contrary, it is a strong player that determines the way hospitals redistribute
resources and even develop capacity (Marmor, 2017). In addition, policy-driven sources of funds
affect strategic planning as they motivate the hospital to keep on working on novel care models,
extend outpatient services, as well as install those technologies that are in line with clinical

THE TRENDS IN THE FINANCING OF US HOSPITAL CARE 24
results and reimbursement priorities, thus, they are also closely linked with financial
sustainability and general public health objectives.
One more significant change has been the introduction of private insurance and value-
based reimbursement systems that have been the result of cost-control policies. In the past,
traditional fee-for-service models would financially reward high utilization; however, in newer
systems, payments are connected to patient outcomes and performance benchmarks, thus
motivating hospitals to engage in the activities of both efficiency and quality. According to the
National Center for Health Statistics (2017), hospitals residing in states with higher rates of
insurance coverage have more financial freedom, especially when reimbursement is linked to
population health metrics, thus being able to facilitate the supply of care that is innovative and
the development of staff. Private insurers are consistently adjusting their agreements to match
the ACOs, bundled payments, and readmission penalties, which have an aggregate effect on the
budgeting and resource planning in hospitals. Such a switch has been instrumental in improving
the 'bridge' between preventive services, data analytics and coordination with outpatient
providers, thus, a more comprehensive approach in patient management has been developed.
Besides, hospitals are also accessing performance tracking on the spot and using the predictive
modeling to attract more income and to lessen the financial risk. The private payers who were
once passive bill-payers are now deeply involved in the negotiation processes that shape the
hospital finance strategies as they put clinical priorities and long-term institutional planning
under their influence as cost and quality pressures intensify.
The growth of private equity, mergers, and philanthropy has changed the hospital
financing landscape, not only for the delivery of the service but also for the twenty-first-century
invention and investment. By the way, the present paper only mentions briefly the influence of

THE TRENDS IN THE FINANCING OF US HOSPITAL CARE 25
private equity, which is so powerful that beyond wondering, we have to delve into discussing
this impact deeply. Marmor (2017) says that through investor-backed acquisitions, financially
distressed hospitals can first of all avoid closure and secondly they draw a kind of capital that
can be administrative restructuring, thus, the latter being at the forefront of technology,
electronic health records, and facility upgrades that they could not do before. Nevertheless, this
injection of money is often accompanied by an expectation of profit, and this may affect the
staffing, the service offerings, or the billing, thus, institutional priorities may be oriented to
higher-margin services. Philanthropy is also benefiting from this transition as it is no longer just
about the one-time gift but rather about established endowments, naming rights agreements, and
local fundraising partnerships that provide a stable and foreseeable revenue base for strategic
projects. Such sources are of high value to nonprofit and research hospitals that depend on mixed
funding and where these sources enable them to construct new wings, take care of specialty
centers, or give a subsidy to the innovation program to maintain the vitality of mission-driven
programs. As per Cutler and Morton (2013), philanthropy and private equity are not substitutes
for public funds but are filling the structural gaps left by uneven reimbursement and rising
operational costs, enabling hospitals to pursue long-term development, clinical excellence, and
community engagement while maintaining financial resilience.
New data-driven reimbursement forms and digital fundraising have changed the
hospital's funding access beyond recognition. According to Househ (2013), digital platforms
have made it possible for hospitals to attract donors, insurers, and patients by implementing
targeted communication strategies and being transparent with outcomes, thereby increasing both
financial support and community trust. Social media and online campaigns have become a vital
support for crowdfunding in such areas as rare disease treatment, research trials, and community

THE TRENDS IN THE FINANCING OF US HOSPITAL CARE 26
health partnerships (National Center for Health Statistics, 2017). Hospitals can now gain access
to a more extensive audience and raise money more quickly. On the institutional level, data
sharing agreements and quality reporting provide hospitals with the opportunity to receive
incentive-based funding that is linked with performance, the rate of rehospitalization, and patient
satisfaction, thus, supporting the culture of accountability and continuous improvement. These
digital channels are not only tools for accountability but also fundraising vehicles which create
feedback loops that help hospitals make operational and strategic decisions. The implementation
of telehealth, electronic health records, and predictive analytics in hospitals makes these systems
more than just clinical assets; they are also reimbursement diversification, targeted financial
planning, and enhanced donor engagement gateways (Ventola, 2015). The integration of digital
technologies empowers hospitals to be financially strong and at the same time, funding is in line
with the measurable outcomes, innovation initiatives, and patient-centered care.
The rise in health conditions and disparities has led to alternative funding models that
concentrate on vulnerable populations. Mokdad et al. (2018) discovered that the geographic and
socioeconomic distribution of chronic diseases is the main factor to local funding initiatives,
such as in behavioral health, dental care, and rural service delivery, thus allowing hospitals to
direct the resources to the areas where the need is greatest. According to the National Research
Council (2012), a health system allocation of resources is gradually more dependent on the
identified access gaps among the population groups that have not been served well. This is
achieved through grants, public-private partnerships, and targeted subsidies, thus creating
mechanisms that go beyond the traditional reimbursement streams. The resources obtained
through oral health access programs, maternal care initiatives, and opioid response funding, for
instance, have become indispensable for hospital departments that are able now to make

THE TRENDS IN THE FINANCING OF US HOSPITAL CARE 27
interventions that are specific and also have specialized staff. Ventola (2015) also mentions that
antibiotic resistance has been the cause of several actions undertaken by the federal and
international sectors, which are infection control infrastructure, surveillance systems, and
antimicrobial stewardship programs, altogether indicating how emerging clinical threats impact
financial planning and capital investment. These new streams, when taken together, are
indicative of the changes in risk profiles that have evolved, public health crises, and social
determinants of health are the factors that have redefined the financial ecosystem for hospitals.
Thus making institutions adopt adaptive strategies that are also beyond the traditionally accepted
payment models and further advance equity, innovation, and community resilience.
Summary and conclusion
This study gave the researcher an opportunity to inquire about the funding trends and the
cash sources of hospitals in the U.S. The study shows that hospital care is one of the largest
sectors of the country's health care system. As of 2018, this part of the system has been allocated
about 33% of the fund. Quantitative research made it clear that the total expenditure in the
country has been on the increase since the 1970s, which means that hospitals are spending more
money than before. Besides that, there are significant changes concerning the sources of
financing. In recent years, it has been noted that other sources such as Medicaid, private
insurance, etc. have evolved leading to a considerable decrease in the out-of-pocket financing.
Also, the research uncovered that the federal government remains the primary source, being the
only one, for the funding of hospital care in the U.S. These changes represent the main shifts that
have been discovered in the hospital care field in the country. According to the survey, hospital
expenditures will continue to exceed the general economic growth of the nation, which is mainly
caused by the growing needs of the people. The findings leave no doubt that the health care

THE TRENDS IN THE FINANCING OF US HOSPITAL CARE 28
financing arrangements should be long-lasting. They should make a compromise between the
affordability, the efficiency, and the accessibility of care. The growth in spending is not merely
due to inflation but also demographic trends, chronic disease management, technological
progress, and regulatory requirements that are both setting the bar higher and increasing the
investment needed in health care. The multiplicity of funding sources is a sign of efforts to
protect hospitals from financial shocks while allowing for greater coverage. Nevertheless, it also
makes financial management more challenging. Future executives and decision-makers should
henceforth ready themselves for a situation where the provision of funds will totally hinge on
performance outcomes, patient satisfaction, and cost-efficiency raking of hospitals.

THE TRENDS IN THE FINANCING OF US HOSPITAL CARE 29
References
Burill, S. (2018). Five Trends That Could Impact Health Care in 2019. The Wall Street Journal.
Retrieved on February 11, 2019 from https://deloitte.wsj.com/cfo/2018/12/12/health-
care-outlook-2019-five-trends-that-could-impact-health-plans-hospitals-and-patients/
Calvert, M., Blazeby, J., Altman, D. G., Revicki, D. A., Moher, D., Brundage, M. D., &
CONSORT PRO Group, F. T. (2013). Reporting of patient-reported outcomes in
randomized trials: the CONSORT PRO extension. Jama, 309(8), 814-822.
Carrera, P. M., Kantarjian, H. M., & Blinder, V. S. (2018). The financial burden and distress of
patients with cancer: understanding and stepping‐up action on the financial toxicity of
cancer treatment. CA: a cancer journal for clinicians, 68(2), 153-165.
Cleverley, W. O., & Cleverley, J. O. (2017). Essentials of health care finance. Jones & Bartlett
Learning.
Curtis, L. A. (2013). Unit costs of health and social care 2013. Personal Social Services
Research Unit, University of Kent.
Cutler, D. M., & Morton, F. S. (2013). Hospitals, market share, and
consolidation. Jama, 310(18), 1964-1970.
Dieleman, J. L., Baral, R., Birger, M., Bui, A. L., Bulchis, A., Chapin, A., ... & Murray, C. J.
(2016). US spending on personal health care and public health, 1996-
2013. Jama, 316(24), 2627-2646.
Househ, M. (2013). The use of social media in healthcare: organizational, clinical, and patient
perspectives. Enabling health and healthcare through ICT, 244-248.

THE TRENDS IN THE FINANCING OF US HOSPITAL CARE 30
Kaiser Family Foundation. (2019). Analysis of National Hospital Health Expenditure. Kaiser
Family Foundation. Retrieved on February 11, 2019 from
http://kff.org/interactive/health-spending-explorer/
Kaiser. P. (2019). Health spending and the economy. Health Systems Tracker. Retrieved on
February 11, 2019 from https://www.healthsystemtracker.org/indicator/spending/health-
expenditure-gdp/
Karanikolos, M., Mladovsky, P., Cylus, J., Thomson, S., Basu, S., Stuckler, D., ... & McKee, M.
(2013). Financial crisis, austerity, and health in Europe. The lancet, 381(9874), 1323-
1331.
Keehan, S. P., Cuckler, G. A., Sisko, A. M., Madison, A. J., Smith, S. D., Stone, D. A., ... &
Lizonitz, J. M. (2015). National health expenditure projections, 1970 –24: spending grew
faster than recent trends. Health Affairs, 34(8), 1407-1417.
Marmor, T. R. (2017). The politics of Medicare. Routledge.
Mills, A. (2014). Health care systems in low-and middle-income countries. New England
Journal of Medicine, 370(6), 552-557.\
Mokdad, A. H., Ballestros, K., Echko, M., Glenn, S., Olsen, H. E., Mullany, E., ... & US Burden
of Disease Collaborators. (2018). The state of US health, 1990-2016: burden of diseases,
injuries, and risk factors among US states. Jama, 319(14), 1444-1472.
Moses, H., Matheson, D. H., Dorsey, E. R., George, B. P., Sadoff, D., & Yoshimura, S. (2013).
The anatomy of health care in the United States. Jama, 310(18), 1947-1964.

THE TRENDS IN THE FINANCING OF US HOSPITAL CARE 31
National Center for Health Statistics (US), & National Center for Health Services Research.
(2012). Health, United States. US Department of Health, Education, and Welfare, Public
Health Service, Health Resources Administration, National Center for Health Statistics.
National Center for Health Statistics. (2017). Health, United States, 2016, with chartbook on
long-term trends in health.
National Research Council, Board on Children, Youth, & Committee on Oral Health Access to
Services. (2012). Improving access to oral health care for vulnerable and underserved
populations. National Academies Press.
Obama, B. (2016). United States health care reform: progress to date and next
steps. Jama, 316(5), 525-532.
Papanicolas, I., Woskie, L. R., & Jha, A. K. (2018). Health care spending in the United States
and other high-income countries. Jama, 319(10), 1024-1039.
Sherman, R. E., Anderson, S. A., Dal Pan, G. J., Gray, G. W., Gross, T., Hunter, N. L., ... &
Califf, R. M. (2016). Real-world evidence—what is it and what can it tell us. N Engl J
Med, 375(23), 2293-2297.
Tacconelli, E., Carrara, E., Savoldi, A., Harbarth, S., Mendelson, M., Monnet, D. L., ... & Zorzet,
A. (2018). Discovery, research, and development of new antibiotics: the WHO priority
list of antibiotic-resistant bacteria and tuberculosis. The Lancet infectious diseases, 18(3),
318-327.
Ventola, C. L. (2015). The antibiotic resistance crisis: part 1: causes and threats. Pharmacy and
therapeutics, 40(4), 277.

THE TRENDS IN THE FINANCING OF US HOSPITAL CARE 32
Yip, W. C. M., Hsiao, W. C., Chen, W., Hu, S., Ma, J., & Maynard, A. (2012). Early appraisal of
China's huge and complex health-care reforms. The Lancet, 379(9818), 833-842.
Zimlichman, E., Henderson, D., Tamir, O., Franz, C., Song, P., Yamin, C. K., ... & Bates, D. W.
(2013). Health care–associated infections: a meta-analysis of costs and financial impact
on the US health care system. JAMA internal medicine, 173(22), 2039-2046.

