


1
Section 1: Foundation of the Study and Literature Review
Introduction to the Study
Data from diagnosed single and multiple chronic conditions indicates that 1 in
every 4 Americans has an underlying chronic condition (Boersma et al., 2020).
According to Bhatt and Bathija (2018), chronic diseases, like diabetes, cancer, and heart
diseases, account for nearly 70% of deaths in the United States. Studies have also shown
that people from lower socioeconomic backgrounds are highly associated with poor self-
reported health outcomes, have reduced life expectancy, and are vulnerable to chronic
diseases (Arpey et al., 2017; McMaughan et al., 2020; Wang & Geng, 2019). Chronic
conditions affect the health of tens of thousands of the country’s vulnerable communities
and consume a considerable proportion of the health care budget in counties and states
(Bhatt & Bathija, 2018). Health care policymakers are challenged to align patient
management with the quality of care received by patients. Health care leaders are also
required to align the delivery of chronic care with the quality metrics.
The purpose of this quantitative study was to examine if patient care quality and
safety are related to hospitals’ socioeconomic status (SES) in Chicago’s acute care
hospitals. The sample included acute care hospitals that provide acute and general health
care to patients in Chicago, Illinois. Ensuring good quality of patient care and high
standards of patient care safety are the primary goals of health care leaders (Freeman et
al., 2020; Gonzalo et al., 2018). SES has been associated with several aspects of health
care services, including determining the quality of health services provided to the
patients, patient insurance coverage, and overall patient outcomes (Call & Miedema,

2
2018; Jordans et al., 2019). Focusing on the state of Illinois was essential to
understanding the impact of SES on health care access and delivery because urban areas
have diverse groups of individuals from different socioeconomic backgrounds. The
results may inform models that can enhance the provision of safe and quality patient care
for diverse urban populations. This understanding may lead to positive social change
through determining whether differential health outcomes are affected by a hospital’s
SES.
In this section, I discuss the background of the topic, problem statement, purpose
statement, research questions, theoretical framework and literature search strategy,
literature review related to key variables and concepts, definitions of terms, assumptions,
delimitations, and significance. The section concludes with a summary of key points.
Background
Urban areas may be excluded from access to the much-needed health care
services due to the continuing transformations in health care (Ahmed et al., 2016; Jin et
al., 2017; Koosters et al., 2018; Sweeney et al., 2018). Currently, the major health care
transformations in the US include implementation of alternative payment models and
introduction of new models of provider organizations (Burns & Pauly, 2018). While these
transformations do not seek to shift risk to providers, they intend to make them more
accountable for the quality and cost of health care. Urban health care systems in Illinois
are not different from any other system across the United States (Freeman et al., 2020;
Gonzalo et al., 2018; Howard-Anderson et al., 2016; Koch & Geller, 2019; Rethy et al.,
2019). Metropolitan areas with low-income populations have prominent disparities in

3
health care quality and safety as compared to areas with high-income populations
(Alhassan et al., 2015; Cheng & Michael, 2014). According to Arpey et al. (2017),
persons from low-socioeconomic backgrounds receive limited access to medications and
health care due to the high costs and limited insurance coverage. While local health care
providers may meet the required standards of providing quality care, low-income
populations are often overlooked, a factor that contributes to increasing inequities in
access to health care (Jordans et al., 2019).
Poverty and health are intrinsically connected. Middle- and low-income
populations require more acute care than those from higher socioeconomic backgrounds
(Arpey et al., 2017; Han et al., 2016; Hewner et al., 2016; Jordans et al., 2019). Changes
in health care dynamics and increased healthcare expenses require providers to develop a
strategy that will enhance the quality of services for patients regardless of race or
financial status (Koosters et al., 2018; Sweeney et al., 2018). Literature on quality and
safety of patient care should underscore the association between hospitals’ SES and the
provision of health care services. There is a gap in literature regarding the relationship
between patient care safety and quality of care with the SES of acute care hospitals in
urban areas. In this study, I sought to close the gap by exploring the relationship between
hospitals’ SES and patient care quality and safety.
Problem Statement
The general problem under study was that the quality and safety of patient care in
urban areas is affected by SES. Studies have shown that due to clinician bias, physicians
give little attention to patients of low SES and are more likely to prescribe generic

4
medication to them (Arpey et al., 2017; McMaughan et al., 2020). The specific problem
was that it was unknown how quality and safety of patient care in Chicago’s hospitals
was correlated to SES (see Call & Miedema, 2018; Jordans et al., 2019). As is the case
with major urban cities, hospitals in Chicago tend to have inconsistent patient
experiences based on their SES (American College of Healthcare Executives, 2022; Bhatt
& Bathija, 2018; Jordans et al., 2019).
Health care is designed to provide patients with the needed care in a safe
environment (Kabisch, 2019). Quality and safety are crucial to providing patients with
the required care. The quality and safety of patient care is a growing concern for U.S.
healthcare systems (Galama & Van Kippersluis, 2019; Garchitorena & Sokolow, 2017;
Kabisch, 2019). There is evidence that significant disparities exist related to patient care
quality and safety based on a patient’s race, ethnicity, and gender (Kabisch, 2019; Koch
& Geller, 2019). SES also contributes to the growing disparities in the quality and safety
of inpatient care. I conducted this study to explore patient care quality and safety in
relation to SES.
Quality and safety of patient care vary according to geographic location (Popescu
et al., 2019). There is a profound disparity in the quality and safety of patient care
between rural and urban regions across the United States (Bhatt & Bathija, 2018). Lack
of quality and safe patient care can lead to increased morbidity and mortality rates,
increased risk of hospitalization, and a significant risk of injury or death in clinical setting
(Arpey et al., 2017). An examination of the quality and safety of patient care can help
with an understanding of how better to improve the health care system and meet the

5
health care needs of patients among vulnerable communities. Growth in this
understanding can lead to improved patient care safety, decreased mortality and
morbidity rates, and enhanced quality of life.
I selected the city of Chicago, Illinois as the designated urban area of research. A
key differentiation for Illinois from the rest of the United States is health care
commercialization (Koch & Geller, 2019). Moreover, available evidence suggests that
despite increased commercialization, health care quality and safety metrics have not been
met for communities from low socioeconomic backgrounds (Jordans et al., 2019). Low-
income populations face unique challenges in obtaining quality and safe patient care
(Arpey et al., 2017; Williams et al., 2010). There is also a paucity of research related to
the link between hospitals’ SES and quality of patient care and safety in Illinois (Call &
Miedema, 2018; Jordans et al., 2019). I conducted this study to provide meaningful and
complementary insights for improving the culture of patient care quality and safety of
health care delivery systems in Illinois.
Purpose of the Study
The purpose of this quantitative study was to examine if patient care quality and
safety are related to hospitals’ SES among Chicago’s acute care hospitals. The study
included three variables. The independent variable was hospitals’ SES while the
dependent variables were patient care quality and patient care safety provided in the acute
care hospitals. The SES of acute care hospitals was determined from Medicare’s
disproportionate share hospital (DSH) designation (Medicare Learning Network [MLN],
2021). According to the Centers for Medicare and Medicaid Services (CMS; 2022), acute

6
care hospitals in urban areas qualify for Medicare DSH adjustment if their bed capacities
are at least 100 and receive more than 30% of their total net inpatient care revenues from
public sources for indigent care (MLN, 2021). Based on the formula applied by CMS,
two categories of acute care hospitals were identified: high-SES acute care hospitals,
which serve high-SES patients, and low-SES acute care hospitals, which serve patients
from disproportionately disadvantaged backgrounds. I used hospital readmission rates for
select conditions to measure patient care quality while the measure of hospital-acquired
infections (HAIs) was used as a proxy measure of patient care safety. Understanding how
quality of patient care and patient care safety are associated with hospitals’ SES is
essential in designing policies for improving health care systems and ensuring vulnerable
populations’ access to quality care.
Research Questions and Hypotheses
I based the research questions on the categorization of acute care hospitals. I
grouped hospitals into two categories: those serving patients of low SES and those
serving high-SES patients. The research questions and hypotheses were:
RQ1: Is there a difference in patient care quality between hospitals of low SES
and hospitals of high SES among Chicago’s acute care hospitals?
H
0
1: There is no statistically significant difference in patient care quality
between hospitals of low SES and hospitals of high SES among Chicago’s
acute care hospitals.

7
H
a
1: There is a statistically significant difference in patient care quality
between hospitals of low SES and hospitals of high SES among Chicago’s
acute care hospitals.
RQ2: Is there a difference in patient care safety between hospitals of low SES and
hospitals of high SES among Chicago’s acute care hospitals?
H
0
2: There is no statistically significant difference in patient care safety
between hospitals of low SES and hospitals of high SES among Chicago’s
acute care hospitals.
H
a
2: There is a statistically significant difference in patient care safety
between hospitals of low SES and hospitals of high SES among Chicago’s
acute care hospitals.
Theoretical Framework
In this study, I used the Donabedian quality framework (DQF) to explore the
relationship between patient care quality and safety with hospitals’ SES among Chicago’s
acute care hospitals. The DQF is used to guide health care workers towards standards of
providing and studying patient care quality (Binder et al., 2021). The DQF of care is
premised on three interlinked structures that are a prerequisite for the provision of high-
quality and safe patient care: structures, processes, and outcomes (LoPorto, 2020).
Ayanian and Markel (2016) indicated that the quality of services can improve when
health care providers remain neutral and increase their detachment levels. Berwick and
Fox (2016) have further suggested that the structure of health care systems affects the
processes and outcomes of patient care. High quality of care is anchored on the extent to

8
which the processes result in desired health outcomes that are informed by professional
skills and knowledge.
The DQF was suitable for this study because it espouses evidence-based insights
on how health care practices in urban environments can be consistently and sustainably
pursued to enhance the delivery of quality and safe health care services (see Wang et al.,
2019). Medical systems in urban areas are likely to have better environments and
facilities than those in rural and semi urban contexts (Bhatt & Bathija, 2018). Urban areas
are also likely to have facilities that require high professional competence and employ
medical staff with enlightened morals. Despite the high medical costs in urban settings,
patients are likely to access high-quality health care information alongside improved
communication. Medical practitioners in urban settings are also associated with improved
care toward patients. These patients can experience efficient and well-coordinated care
(see Wang et al., 2019). Patients are also likely to report higher levels of safety and better
health outcomes than those in the medical systems in rural and low-income areas.
I also used the Andersen behavioral model of health services in this study to
determine the extent to which patient care safety and quality can contribute toward long-
term use of services and supports (see Travers et al., 2020). The Andersen model can be
applied as an economic framework that explores patient needs, enabling environment,
and predisposing factors (Hong et al., 2019; Pilar et al., 2020). The model was
appropriate for this study because it provided a theoretical lens through which to explore
the relationship between SES and patient care quality and safety. The model was
originally developed in the 1970s to consider how policies, resources, and demographic

9
factors are related to health care quality (Hong et al., 2019). In the model, it is suggested
that that SES is highly associated with the quality and safety of care as well as that
patient-centered factors, such as financial constraints and distance to a health care
facility, could affect patients’ access to health care. More recent conceptualizations have
indicated that personal demographic variables, such as SES, may be related to patient
perceptions of the quality and safety of care received at health care facilities (Hong et al.,
2019; Pilar et al., 2020). The Andersen model was important for this study because it is
used to consider the variables of SES and provided a framework for exploring how
systematic policies may impact patients differentially (see Pilar et al., 2020). In using the
model, I articulated the link between patients’ SES and the quality and safety of health
care received.
Nature of the Study
In this study, I used a quantitative approach and a cross-sectional design to
investigate if statistically significant differences in patient care quality and safety exist
between low-SES and high-SES acute care hospitals in Chicago. Numerical patient data
were accessed from the Illinois Department of Public Health (IDPH). I used secondary
data for this study to enhance the external validity of the research due to the possibility of
accessing a large data set. The independent variable was the SES of acute care hospitals
while the dependent variables were patient care quality and patient care safety. The target
population for the study comprised acute care hospitals within the state of Illinois.
Hospitals that serve a significantly disproportionate number of low-income patients were
categorized as Medicare DSH hospitals (see MLN, 2021). These hospitals were

10
considered as low-SES hospitals because they majorly serve patients from low-SES
backgrounds (Hsieh & Bazzoli, 2012). Conversely, patients from stable socioeconomic
backgrounds are likely to use non-Medicare DSH hospitals (McMaughan et al., 2020).
Such acute care facilities were regarded as high-SES hospitals. The acute care hospitals
were categorized as either low-SES or high-SES hospitals based on the defining
qualifications for the alternate special exception for DSH adjustment payments (see
MLN, 2021). The data on patient care quality and safety was categorized into two groups:
Medicare DSH and non-Medicare DSH hospitals. To analyze the data, I used independent
samples t tests. An independent samples t test is conducted to compare the mean values
between two unrelated categories (Carlson & Winquist, 2017, p. 316).
Literature Search Strategy
I performed a search for relevant articles, documents, and periodicals in different
databases to complete the review of related literature for this study. The databases and
search engines used included: Google Scholar, Psych Articles, Science Direct, EBSCO,
JSTOR, PubMed, and Educational Resource Information Center. In performing the
database search, I used the following keywords related to the topic of this study:
Donabedian model, Andersen model, urban healthcare and challenges to healthcare
systems, patient care quality, and patient care safety. The search terms were also used in
conjunction with each other to generate more specific and relevant search results.
I also reviewed the reference lists of the relevant articles to determine possible
additional studies to include. Relevant articles were included to establish the components
of the theoretical framework, research problem, and research phenomenon. Most of the

11
articles and documents included in this review were published between 2017 and 2021
(i.e., at least 85%), except for a few (i.e., less than 15%) seminal articles that were
published before 2017.
Literature Review Related to Key Variables and Concepts
Health care systems in urban areas are characterized by more complex systems,
causing more health problems in the urban settings than in the rural areas (Rath, 2020).
With high urban population growth, the need for equal access to quality health care and
fair distribution of health care services is a concern that must be addressed (Rezaee et al.,
2021). In this literature review, I explored important aspects of urban health care systems.
The subsections in this literature review are focused on (a) the Donabedian framework
and health care, (b) the Andersen model of health care utilization, (c) importance of
patients’ SES in health care, (d) importance of patient care quality and safety, (e) patient
care quality and safety in urban areas, and (f) primary challenges for urban health care
systems.
Donabedian’s Framework and Health Care
I used the DQF as a guide in exploring the phenomenon of interest, which was the
association of hospitals’ SES with patient care quality and safety in Illinois. Based on the
DQF, structural measures have direct influences on process measures, which, in turn,
have a direct influence on the outcome measures of health care (Allen-Duck et al., 2017).
The DQF has been used to explain the path of previous research and ground it in
theoretical constructs (Casanave & Li, 2015; Cohen & Shang, 2015). According to Allen-
Duck et al. (2017), the DQF is ideal for exploring outcomes that intersect with external

12
variables, including hospitals’ SES. The DQF has been used to explore the upholding of
safe, quality, and effective medical practices in medical settings (Ayanian & Markel,
2016).
Medical systems in urban areas are likely to report higher medical costs, better
communication and information, and caring attitudes from staff alongside emotional
support (Wang et al., 2019). Patients in urban settings are also likely to post higher levels
of satisfaction and better health outcomes compared to those in medical systems within
other contexts. The DQF specifically focuses on evaluating the quality of physician-
patient interactions (Allen-Duck et al., 2017). Thus, the model aligned with the current
study in which I investigated how medical systems in urbanized areas sustain continuous
quality and safety improvements (see Casanave & Li, 2015). The current study employed
the outcome measures of the DQF because health care providers within urban contexts
often have to deal with effective organization and management of quality improvements.
The DQF’s process measures provided a lens for understanding how evidence-based
practices in health care can consistently and sustainably support the delivery of high-
quality and safe patient care.
Andersen Model of Health Care Utilization
The Andersen model has been widely used to explore health service use across
different diseases and multiple areas of the health care system (Babitsch et al., 2012). The
Andersen model is a framework that is used to explore patient needs, enabling elements,
and predisposing factors (Hong et al., 2019; Kabir, 2021; Pengid et al., 2022). Hong et al.
(2019) further claims that finances are an enabling factor listed within the model and that

13
enabling factors are important because they determine the ability of an individual to pay
for health care through income or financial assets at their disposal. Third-party economic
support through health insurance is also considered as an enabling element (Andersen &
Davidson, 2007). The Andersen model was important for this study because I used it to
expound on the roles of SES as a variable of this study and it provided a framework for
exploring how systematic policies may impact patients in different ways (see Pilar et al.,
2020).
Importance of SES in Health Care Context
SES may be translated into several aspects of an individual’s living and
relationship within a community (Øversveen et al., 2017). In the field of health care, a
person’s SES is a determinant of health status (Øversveen et al., 2017; Ruiz-Pérez et al.,
2021). People from high socioeconomic backgrounds have access to better options of
health care services compared to their counterparts from low-SES backgrounds
(Øversveen et al., 2017; Ruiz-Pérez et al., 2021).
Researchers have explored the role of SES in health and the quality of care
received. Øversveen et al. (2017) focused on social inequality in rethinking the causal
relationship between SES and health. The authors claimed that the relationship between
SES and the health of a person is not static. Qualitative data must be collected in
conjunction with quantitative data that considers SES and health as dynamic variables
(Øversveen et al., 2017). However, the authors did not completely validate their findings
through real-life settings or did they explore the factors related to patient care quality and
safety. In another study, SES and the health status of individuals were explored within the

14
context of a financial crisis (Ruiz-Pérez et al., 2021). Persons who had less to spend on
health services had poor mental health (Ruiz-Pérez et al., 2021). These studies
highlighted the role of SES in the health of individuals, which is related to the topic of the
current study. These studies, however, were not focused on explicating the interplay of
patient care quality and safety in the context of SES, which were the specific variables of
interest in the current study.
Socioeconomic inequity has also been explored in the context of access to health
care services (Sibeudu et al., 2017; Tumin et al., 2018). According to Donahoe and
McGuire (2020), SES is a fundamental driver of health because it features the main
resources that are crucial in avoiding risks and lessening the impact of diseases. Families
and individuals from high-socioeconomic groups have a high tendency to avail for
routine immunization services as compared to those belonging to low-SES populations
(Sibeudu et al., 2017). The main barrier to accessing health care services by individuals
from low-socioeconomic backgrounds, especially immunization, is the cost factor (Arpey
et al., 2017; Donahoe & McGuire, 2020). The high cost of accessing health care can
impede individuals from low-SES backgrounds from accessing most acute health care
services. In addition to the cost of the health care services, additional expenses, such as
the transport cost incurred when availing themselves or their children for vaccination, are
a key concern for people from low-SES backgrounds (Sibeudu et al., 2017). However,
these findings are not focused on patient care quality and safety in the context of SES.
The impact of a community’s socioeconomic inequality on the provision of health
care services has also been previously explored by researchers. Tumin et al. (2018) found

15
that communities or counties with prevalent socioeconomic inequality, compared to
people from socioeconomically equal communities or counties, have a wide array of
unmet health care needs as measured through income inequality metrics. Nonetheless,
Tumin et al. only focused on a small population in a single state, limiting the study’s
external validity. Including a larger scope and population in the same study would be
more beneficial for making valid conclusions about the importance of SES in the context
of accessing health care services.
The findings of the different studies that have focused on the role of SES in
accessing health care suggest that ability to pay is crucial insofar as accessing health care
services is concerned (Donahoe & McGuire, 2020; Øversveen et al., 2017; Ruiz-Pérez et
al., 2021; Sibeudu et al., 2017; Tumin et al., 2018). Those individuals with the capacity to
pay are more likely to gain access to different health care services. Having a wider gap in
SES within a community is a significant predictor of the ease of access to good quality
health care services (Sibeudu et al., 2017; Tumin et al., 2018). For those with limited
monetary resources, accessing good quality health care remains a significant challenge.
Importance of Patient Care Quality and Patient Care Safety
Patient care quality and patient care safety are two of the most important
considerations when assessing the quality of health care services being provided (World
Health Organization, 2019). In systematic reviews that explored the different factors
related to quality and safety of patient care, researchers found that the burnout of health
care professionals has a significant impact on patient care safety (Garcia et al., 2019; Han
et al, 2016; Hewner et al., 2016; Jordans et al., 2019; Lawati et al., 2018). A high burnout

16
level among nurses and physicians is common and is associated with external factors,
including ineffective interpersonal relationships and high workload. To enhance patient
care safety, health care facilities must have organized workflows that generate autonomy
for health care professionals (Garcia et al., 2019). In another systematic review, Lawati et
al. (2018) highlighted the importance of conducting an assessment of a culture of safety
in primary care, suggesting that the approach is helpful in understanding the safety-
related perceptions of health care providers. Garcia et al. (2019) and Lawati et al. (2018)
have established the importance of measures of patient care safety in the provision of
high-quality health care services; however, their studies were not complete in exploring
patient care safety within the context of SES of patients.
Patient care has been highlighted as an important aspect to the health of
individuals, especially immigrants (Wylie et al., 2019). Similar to the studies of Lawati et
al. (2018) and Garcia et al. (2019), Wylie et al. (2019) reported the importance of patient
care in the field of health care services. The implication of SES to patient care has not
been fully established in these studies. Wylie et al.’s study was more focused on quality
of patient care for ensuring the good mental health of immigrants rather than the factors
that influence the patient care of individuals.
Further research by Stockwell et al. (2019) explored contributing factors to the
disparities in in-patient safety for children in hospitals with a focus on the cases of
adverse effects among patients. They found extant disparities in the quality and safety of
health care between hospitalized children from the racial majority (i.e., non-Latino,

17
White) and racial minority. Disparity in health care experiences among children patients
has also been associated with their SES (Stockwell et al., 2019; Wylie et al., 2019).
This indicates that patient care quality and safety are important measures of the
quality of health care services. Researchers have established different predictors of
patient care safety and quality of care. However, studies on the quality and safety of
patient care did not include exploration of patient care safety in relation to the SES of
patients in urban areas.
Primary Challenges for Urban Health Care Systems
This study was built on the findings of previous research that investigated the role
of quality and safety in the improvement of health care systems. Different researchers
have explored the urban health care system (e.g., Adams, 2017; Amoah et al., 2018; Du
et al., 2020; Liu et al., 2018; Unruh & Hofler, 2016; Zhang et al., 2017). Amoah et al.
(2018) explored the nuances related to accessing health care for urban and rural
populations. Their study focused on understanding the hindrances to accessing health
care, finding that rural dwellers are often at a disadvantage compared to urban dwellers.
Amoah et al. indicated that urban residents have the capacity to easily access health care
services while disadvantaged populations, such as those in rural areas, are continually
deprived of easy access to health care services. Zhang et al. (2017) also explored health
care access issues, with a primary focus on urban and rural areas in a developing country.
Through a longitudinal study, the authors found that older adults in rural areas have
higher cases of reported inadequacies in access to health care when compared to older

18
adults in urban areas. Zhang et al.’s findings were consistent with Amoah et al.’s as both
reported that rural areas have poorer access to health care compared to urban areas.
Urban areas are characterized by more job opportunities, better education, and
more choices of entertainment (Adams, 2017). However, these characteristics of urban
areas lead to a higher density of the population, and as a result, access to health care
services may be challenging for patients in such settlements. This finding contradicts the
results of Amoah et al. (2018), who reported that people residing in rural areas have
limited access to high quality and safe patient care. The advantages of more available
jobs and economic activities could mean poor health outcomes due to resource
constraints that overwhelm the urban health care system (Adams, 2017; Amoah et al.,
2018).
One of the primary challenges in accessing health care among low-income
communities is the means of transportation (Du et al., 2020). Older adults in suburban
areas tend to rely on buses and walking when seeking medical treatment. For longer
distances, the financial status of the individual manifests in their chosen mode of
travelling, wherein people from high-income families can use private cars rather than
using public means to get to the hospital (Du et al., 2020). Overall, Du et al.’s (2020)
findings revealed the prevalence of significant differences between accessing health care
in rural and urban areas. Du et al.’s study included patient populations outside the United
States, which reduced its external validity. In a related study, Liu et al. (2018) found that
the choices of health care facility in rural and urban areas in China influenced the quality
and safety of health care received by patients. In rural areas, patients choose township

19
health care facilities by default, with the possibility of being transferred to higher-level
facilities when necessary. Patients in urban areas chose higher-level facilities by default
whenever seeking medical treatment. Both Du et al. and Liu et al. highlighted the
differences in the decisions made by patients in rural and urban settings with regard to
health care access; however, the unique challenges to urban area health care services
were not explored completely in the two studies since none of them looked at differences
in patient care quality and safety between urban and rural health care facilities.
The primary challenges for most health care systems in urban regions include
management of quality and safety improvements and maintenance of effective
organizations (Unruh & Hofler, 2016). Most acute care hospitals have significant gaps in
quality indicators (Unruh & Hofler, 2016). Unruh and Hofler (2016) assessed the
predictors of gaps between the best possible and actual quality scores. For children, one
of the main sources of health care services is their respective public schools; however,
these schools and their health service personnel are often ill equipped to provide quality
health care, especially in low-income, urban communities (Kuriyan et al., 2021).
Additionally, Unruh and Hofler acknowledged that the direction of association with gaps
was not homogenous across outcomes; however, their study was not specific to hospitals
located in an urban locality. The current study built on Unruh and Hofler’s findings to
investigate the interrelationship of patient care quality and safety with the SES of acute
care hospitals.

20
Patient Care Quality and Safety in Urban Areas
Researchers have identified several gaps in empirical research regarding the
quality and safety of patient care in urban areas (Garcia et al., 2019; Lawati et al., 2018;
Han et al, 2016; Hewner et al., 2016; Jordans et al., 2019). Generally, it is assumed that
urban populations are financially stable and can afford health care services; however, an
increase in urban population leads to a rise in communicable and non-communicable
diseases (Fausto et al., 2017). The urban population is increasingly prone to diseases due
to unsanitary living conditions. The quality of air in urban settings is retrogressively poor
due to disproportionate pollution while more than 40% of the urban residents do not have
access safe and clean drinking water (World Health Organization, 2021). Quality and
safety are constantly evolving due to demographic factors, such as aging populations,
technological advancements, developments in medical treatments, and shifting
preferences of core stakeholders (Han et al., 2016; Hewner et al., 2016; Jordans et al.,
2019; Unruh & Hofler, 2016).
Empirical studies have revealed extant inequities in the provision of quality health
care for low socioeconomic groups in urban and suburban settings (Scholaske et al.,
2018; Van Hecke & Heinen, 2017; Yaya et al., 2017). Previous studies have illustrated
that SES, gender, and race influence access to quality and safe health care (Galama &
Van Kippersluis, 2019; Garchitorena & Sokolow, 2017; Kabisch, 2019). In urban and
suburban settings, resources and infrastructures are adequate; however, a portion of the
population suffer from apparent lack of quality care due to the impact of their
socioeconomic, gender, and ethical status (Alhassan et al., 2015; Etchin et al., 2019).

21
Furthermore, health care costs (for example, co-pay or self-pay insurance) are
increasingly becoming expensive for ordinary persons (Allen-Duck et al., 2017). Poverty
and health are intrinsically connected; moreover, low health quality is often linked to low
SES. People from low-SES backgrounds often find themselves in the state of needing
high-quality health care compared to those from more affluent background (Han et al.,
2016; Hewner et al., 2016; Jordans et al., 2019). In this study, the focus of the exploration
will be the gap in research about the relationship of patient care quality and patient care
safety to the SES of patients in the city of Chicago, Illinois.
Operational Definitions
Defining terminologies used in a study is essential in enhancing intelligibility of
the study to its audience. This subsection presents the operational terms used throughout
this study and supported by literature:
Acute Care Hospital: The Centers for Medicare and Medicaid (n.d) defined acute
care hospital as a “hospital that provides inpatient medical care and other related services
for surgery, acute medical conditions, or injuries,” especially for short-term conditions
that may require emergency attention (p. 1). They include health care facilities designed
to improve health care outcomes through active diagnosis, treatment, and rehabilitation of
sick persons within a short duration (Huber et al., 2020).
Disproportionate Share Hospitals (DSHs): DSHs serve patients from significantly
disadvantaged backgrounds, which make them eligible for Medicare’s DSH payment
adjustments to compensate for the cost of providing care to uninsured patients (MLN,
2021).

22
High SES Hospitals: High SES hospitals refer to those acute care hospitals that
are not eligible for Medicare DSH revenue adjustment and serve patients from high
socioeconomic backgrounds.
Hospitals: Hospitals are institutions that are primarily designed, staffed, and
equipped to promote, maintain, and restore the health of patients through proper
diagnosis, treatment, and rehabilitation (Abubakar & Kathuria, 2020). The hospitals of
interest for this study were acute care hospitals in the city of Chicago.
Hospitals’ Socioeconomic Status (SES): Hospitals’ SES was the independent
variable for this study and was determined from Medicare’s DSH categorization.
Hospitals that serve a disproportionate number of patients from low socioeconomic
backgrounds are eligible for Medicare DSH payment adjustment for indigent care (MLN,
2021). Patients from low socioeconomic backgrounds are characterized by limited
education, income, and financial security. The CMS designation of hospitals as either
Medicare DSH or non-Medicare DSH hospitals was used to categorize acute care
hospitals into low SES and high SES hospitals respectively. A Medicare DSH hospital
receives more than 30% of its net inpatient revenue from state and local government
sources. Conversely, non-Medicare DSH hospitals are not eligible for DSH adjustments
as they attend to patients who are economically well-off. In that vein, non-Medicare DSH
hospitals were considered high SES hospitals.
Hospital-Acquired Infections (HAIs): HAIs are preventable illnesses that occur
within 48 hours of patient admission or 30 days after the patient has been admitted and
put on continued care management at the nearest health care facility (Haque et al, 2018).

23
HAIs are infections developed by a patient in the course of receiving treatment and can
lead to the deterioration of health outcomes. It is thus an important proxy of patient care
safety.
Low SES Hospitals: In the operationalization of this study, low SES hospitals are
those hospitals eligible for Medicare DSH revenue adjustment by the fact of serving
patients from disproportionately disadvantaged backgrounds and receive more than 30%
of the total inpatient revenue for indigent care from the state.
Patient Care Quality: Patient care quality is the assessment and provision of
effective and safe care that is reflected in a culture of excellence, resulting in the
attainment of optimal or desired health outcomes (Gqaleni et al., 2020; Puni & Hilton,
2020). Patient care quality was used to conceptualize one of the dependent variables
related to the research questions of this research. The Institute of Medicine (IOM) defined
quality of health care in the perspective of norms, practices, and standards that bestow
desirable health outcomes in consistence with nursing and professional standards
(Mitchell, 2008). This definition connects quality of health care to several indicators that
demonstrate health-promoting behaviors, achievement of high standards of self-care, and
health-related quality of life. Thus, the current study focused on the rate of 30-days
readmission rates in the acute care hospitals to determine the quality of health care
provided in those specific healthcare facilities. The readmission rates give insight into the
quality of hospital’s input in preventing post-treatment complications and educating
patients on how to self-manage their conditions after being discharged.

24
Patient Care Safety: Patient care safety refers to the prevention of harm, errors,
and adverse events to patients receiving healthcare (Cuomo et al., 2021). In this study,
patient care safety was one of the dependent variables used in answering the research
questions. The IOM has defined it as a system of care delivery that (a) ensures prevention
of errors, (b) learns from its errors, and (c) is anchored on the culture of safety that
comprises healthcare professionals, providers, and patients (Mitchell, 2008). The
practices that espouse patient care safety are those that reduce the incidence of harm to
patients within the context of medical care provision across medical conditions and
diagnoses. In this study, patient care safety was determined using HAIs. HAIs result in
unanticipated health outcomes that often add unnecessary burden to the patient, the health
care facility, and relatives of the patient (Haque et al., 2018). The IOM has identified
HAIs as a crucial indicator for the safety of patient care and recommended for mandatory
reporting of adverse health events by acute care facilities, which means that public
scrutiny of health care facilities can help in preventing the incidence of such infections
(Collins, 2008). As HAIs are generally preventable, it was treated as a major metric of
concern in the measurement of safety of care at any given acute care hospital.
Patients’ Readmission Rates: This term refers to the percentage of patients who
return to the health care facility within 30 days of discharge from the hospital (Ferro et
al., 2019). A reduction in inpatient readmission rates in a hospital is an indication of
system wide implementation of hospital initiatives targeted at improving the quality of
care.

25
Urban Area: Urban area refers to at least one aggregate of metropolitan counties
in a state (Kassens & van der Meulen Rodgers, 2019).
Assumptions
Study assumptions are the researcher’s predispositions that are deemed factual
without validation or confirmation (Theofanidis & Fountouki, 2018). A key assumption
of this study was the use of only one factor to represent each of the two dependent
variables. One factor (readmission rates) was used to represent the patient care quality
while HAIs were used to measure patient care safety. The use of one indicator for each of
the variables was based on the assumption that one factor can act as a proxy for all of
quality or safety indicators. The other assumption was that the secondary data that were
used for this study are accurate and reflected the variables of interest. I also used cross-
sectional data accessed from public health databases. Using publicly available data is
both economical and time saving (Wickham, 2019). However, I did not have control over
the certainty and validity of data collection measures that were employed. The other
assumption I made in this study was that the Coronavirus (COVID-19) pandemic had
minimal impact on the accuracy of health care data. By the beginning of June 2022,
already the world had lost more than 6 million lives with over 500,000,000 infections
globally as a result of the COVID-19 health crisis (World Health Organization, 2022).
The impact of the COVID-19 pandemic, especially on the utilization of health care
services, could affect the accuracy of data due to profound health care inequities that
were exacerbated by the pandemic (Moynihan et al., 2021; Zhang et al., 2020). To reduce
the impact of the COVID-19 pandemic on the accuracy of the reported data, binary

26
logistic regression was performed to ascertain the accuracy of the model in determining
the association. I also excluded cases of outliers (missing data or where the values were
nil) based on the assumption that they do not impact data accuracy.
Scope and Delimitations
Delimitations are boundaries that researchers set to make the research feasible.
The first delimitation of this study was the focus of the phenomenon, which was aligned
with the topic and problem of the study: patient care safety and patient care quality of
acute care hospitals in urban areas. The phenomenon is based on the problem of the
study: it is unknown how the quality of care and patient care safety are related to the SES
of Chicago’s acute care hospitals. The study did not include or explore other phenomena.
Secondary data were used to collect adequate information required to address the
research questions. New or primary data were not collected for the study.
Limitations
The limitations of this study included elements that possibly impacted the results
of data collection and analysis. They included the possibility that the proposed data
sources did not avail sufficient information to address the research questions. In
particular, a large sample size could have provided a more meaningful data to enhance
the understanding of how SES, quality of care, and patient care safety are related.
Notwithstanding, I made significant effort to ensure that the collected data were
appropriate for addressing the research questions. The second limitation was the
possibility of the researcher’s bias impacting the findings of the study. Regarding this
concern, a standardized method that precluded researcher’s bias error was considered for

27
data collection and analysis. Each step of data collection was followed carefully to ensure
that these limitations did not impact data analysis and the ultimate findings of the study.
The third limitation of this study was the use of a cross-sectional research design. While a
longitudinal design could have provided an elaborate understanding of the relationship
between the variables in this study, the cross-sectional design was preferred due to cost
factor and time. Limited resources did not allow me to conduct a longitudinal study.
Nonetheless, this study will pitch opportunities for future researchers who may wish to
explore this topic using longitudinal design and to study whether there is any cause and
effect relationship between the variables of interest. The use of only one factor to
represent either patient care safety or patient care quality could have also posed
limitations to this study. However, it was assumed that one indicator can be used as a
proxy for all other factors that determine patient care quality and patient care safety.
Significance of the Study
Several studies have illustrated a link between SES and quality of health care and
safety of patient care (Galama & Van Kippersluis, 2019; Garchitorena & Sokolow, 2017;
Kabisch, 2019). However, there is a dearth of research assessing possible differences in
patient care quality and safety between low SES and high-SES acute care hospitals in
Chicago. The exploration of the status of patient care safety and patient care quality
between Medicare DSH and non-Medicare DSH hospitals can provide useful information
for health care stakeholders in Chicago. Professionals and health care workers, such as
nurses and clinicians, may benefit from positive social change and understand the link
between hospitals’ SES and the quality and safety of health care. Based on their SES,

28
patients may know what to expect in terms of patient care safety and quality of health
care when they visit acute care hospitals. Policy makers can also use this information to
justify the appropriateness of the current health care systems to meet the need of current
and future populations.
Reviewing the relationship between SES and access to health care that is
characterized by high quality and safety can also provide important information for the
management of age-related chronic diseases as there is a rapid increase in aging
populations in urban areas (McMaughan et al., 2020). Cases of chronic and acute
conditions are expected to increase due to the expanding population of Illinois’ urban
areas (Eathington, 2010). The aging population and increasing cases of patients with
chronic disease need regular care regardless of their SES. The results of this study may be
helpful in designing health programs that cater for patients from diverse socioeconomic
backgrounds. Additionally, the findings of this study might help address a crucial gap in
literature regarding the relationship between quality and safety of health care with
hospital’s SES.
Summary and Conclusion
This study sought to understand the relationship between patient care quality and
patient care safety with socioeconomic status of acute care hospitals in Chicago’s urban
areas. The specific problem of this study is that it is unknown how patient care quality
and patient care safety in Chicago’s acute care hospitals are related to hospital’s SES.
This is consistent with the purpose of the study, which is to examine if patient care
quality and safety are related to hospitals’ SES in Chicago’s acute care hospitals. The

29
study included three variables: hospitals’ socioeconomic status (independent variable)
patient care quality (dependent variable) and patient care safety (dependent variable).
SES of the hospitals was categorized into two groups based on the qualifying criteria for
consideration as DSHs. The DQF was used to gain insights into the quality of patient care
in hospitals. Additionally, the Andersen model was used to provide a theoretical lens for
exploring the relationship between quality and safety of patient care and SES.
Several studies have examined the association between SES and quality and
safety of care provided in acute care hospitals. However, there is a dearth of evidence on
the association between patient care quality and patient care safety with hospitals’ SES.
In Section 2, I will provide the study’s outline for the possible relationship between
patient care quality and patient care safety with hospitals’ SES in Chicago’s acute care
hospitals. The section will cover the research design and rationale, methodology, sample
selection and procedure, instruments and data collection procedures, threats to validity,
data analysis, and limitations of the study.

30
Section 2: Research Design and Data Collection
The purpose of this quantitative study was to examine if patient care quality and
safety are related to hospitals’ SES in Chicago’s acute care hospitals. This section
includes a detailed discussion of the selected research design and a justification for using
a quantitative methodology for the study. This discussion also includes information about
the target population, sampling procedures, data collection procedures, and
operationalization of the constructs. After the methodology subsection, I identify
potential threats to the internal and external validity of the study’s results and outline the
ethical procedures and standards that were followed throughout the project. The section
ends with a description of the limitations and a summary.
Research Design and Rationale
In this study, I used a quantitative methodology to examine the relationship
between patient care safety and quality and the SES of acute care hospitals in Chicago,
Illinois. Hospitals’ SES was the independent variable, while patient care quality and
patient care safety were the dependent variables. Secondary data for the independent
variable were obtained from the Illinois Department of Healthcare and Family Services
(HFS) database. The data were gathered with reference to the guideline for hospitals’
qualification for DSH payment adjustments as outlined by CMS.
Hospital data were grouped into two categories: high-SES and low-SES hospitals.
A hospital qualifies for Medicare DSH payment adjustment using the alternate special
exception if it (a) is found in an urban area, (b) has 100 or more beds, and (c) can prove
that revenue adjustments from state and local government sources surpass 30% of their

31
total net inpatient revenues for providing health care to uninsured persons (CMS, 2022;
MLN, 2021; Popescu et al., 2019). Patients from low socioeconomic backgrounds often
have low levels of education, struggle with income needs, and lack financial security
(Arpey et al., 2017). Any hospital that receives more than 30% of their total inpatient
revenue from state or local governments’ sources serves a disproportionate number of
low-income patients. In this study, I referred to such hospitals to as low-SES hospitals
and referred to those that receive less than 30% of their inpatient revenues from state and
local government resources as high-SES hospitals. The Illinois Department of HFS
(2022) database provides a list of facilities eligible for DSH reimbursement under the
hospitals’ reimbursement notifications. I used the determinations for DSH payment,
Medicaid percentage adjustment (MPA), and Medicaid high volume adjustment (MHVA)
to identify the 20 acute care hospitals in Chicago, Illinois that were included in this study.
The 2019 determination used as the focus of this study was for data finalized for the rate
year of 2019.
I did not ignore the effects of the COVID-19 pandemic on the data and health care
workload. The COVID-19 pandemic disproportionately affected communities from low
socioeconomic backgrounds because health care services in low-SES hospitals were
overstretched beyond capacity (World Health Organization, 2021). The COVID-19
pandemic disrupted service delivery in both low- and high-SES hospitals due to the
increase in cases that were not reported or could not be reported due to insufficient health
care services. However, the most affected communities by the disruption resulting from
the health crisis during the COVID-19 pandemic were those relying on health care

32
services from low-SES hospitals (Tuczy ´nska et al., 2022; Zhang et al., 2020). As such, I
outlined a raft of measures for rigorous analysis of the COVID-19 data to reduce errors in
reporting (Stoto et al., 2022). For instance, the secondary data utilized in this study were
collected before the outbreak of the COVID-19 pandemic. This study was also guided by
the scope of the study, which was to find out whether there is a significant difference in
patient care quality and safety between low-SES and high-SES acute care hospitals in
Illinois. During data analysis, I made attempts to reduce the effect of the COVID-19 case
load on the accuracy of the data by simulating differences in the data reported before and
after the pandemic. The outliers were considered as exceptions and excluded during data
analysis. Also, I noted assumptions and delimitations of the study to avoid diverging
from the study’s purpose.
I obtained data for the dependent variables from the IDPH database. The IDPH
database provides a publicly accessible database, the Illinois Hospital Report Card and
the Consumer Guide to Health Care. Links provided by the IDPH were used to access
additional information on quality and safety standards at different hospitals in Illinois
(CMS, 2022). I then compared quality and safety indicators across acute care hospitals.
The categorization of hospitals into Medicare DSH and non-Medicare DSH hospitals was
first done to identify the 20 hospitals (i.e., 10 non-Medicare DSH and 10 Medicare DSH
hospitals) that satisfied the inclusion criteria set by CMS on eligibility for DSH payments
(CMS, 2022; Illinois Department of HFS, 2022).
I derived data on patient care safety and quality from the IDPH’s Division of
patient safety and quality. The IDPH’s Division of Patient Safety and Quality ensures

33
transparency in the provision of health care and oversees the development and
implementation of programs to collate health care provider data for the purposes of
reviewing and improving the quality and value of health care provided to the residents of
Chicago, Illinois. Specific factors were used as proxies for all other indicators that
contribute to the quality and safety of care. The two proxy factors of dependent variables
used in this study were HAIs and patients’ readmission rates.
I measured quality of care using hospital readmission rates. According to Mitchell
(2008), quality care is effective and timely, thus suggesting that high-quality care can
promote reduction in patients’ readmission rates. Patients’ readmission rates have also
been shown to determine the quality of care received from acute care hospitals (Hu et al.,
2014). I, therefore, assumed that hospitals that provided a high quality of health care
provided better health care services and had few cases of patient readmissions for the
select conditions.
I used HAIs as a proxy of patient care safety. HAIs are infections acquired by
patients in the course of treatment at an acute hospital (IDPH, 2021). HAIs are
preventable illnesses that occur within 48 hours of patient admission or 30 days after the
patient has been admitted and put on continued care management at nearest health care
facility (Haque et al., 2018). They include the type of infections that develop during the
course of health care treatment and can cause significant deterioration in patients’ health
outcomes (Collins, 2008). HAIs are a major concern in patient care safety because they
can result in increased morbidity, mortality, costs, and extended hospital stays for
patients (Haque et al., 2018, p. 2327).

34
I compared the two variables of patient care quality and safety from both
categories of hospitals. Since there were two categories of data being sought per each
group of hospitals, averages were used to determine the scores for each factor. The data
used for analysis was from October 2018 through September 2019 for consistency with
the hospitals’ SES data timeline. Each hospital had an average quality score. Having one
score of performance in terms of quality and safety of care allowed for comparison of
hospital performance between high-SES hospitals and low-SES hospitals. This gave two
scores for each variable: (a) patient care quality score in high-SES hospitals and patient
care quality in low-SES hospitals and (b) patient care safety in high-SES hospitals and
patient care safety in low-SES hospitals. I used a two-sample t test to test whether the two
averages (i.e., scores) were equal.
I used an independent sample t test to compare the mean values of health care
quality and safety between Medicare DSH and non-Medicare DSH hospitals. An
independent samples t test is used to compare means between two groups that are not
related (Carlson & Winquist, 2017; Gilchrist & Samuels, 2014). To test the hypotheses
posed in the study, I conducted two independent t-test analyses. Regarding the first
hypothesis, the mean value of patient care quality between low-SES hospitals and high-
SES hospitals were compared to determine if a significant difference existed between
them. For the second hypothesis, patient care safety was compared between low-SES and
high-SES hospitals in Chicago, Illinois to determine if there was a statistically significant
difference between them.

35
Quantitative data are desired for cases where the focus is on numerical
measurement of the relationship between variables (Eyisi, 2016). A qualitative approach
was not appropriate for this study because the objective of this study was not to explore
the details of how or why questions regarding the participants’ experiences of patient care
quality and safety. Qualitative methodology is used when research questions require
opinions of the respondents of interest (Yin, 2017). In qualitative studies, the objective is
to study the nuances and intricacies of a phenomenon and to obtain narrative descriptions
of the participants’ experiences and perceptions (Lund, 2021). Data for qualitative
designs are collected through interviews, observations, focus groups, questionnaires, and
from similar methods that focus on descriptive analysis. Qualitative data can be in many
forms, like in texts, images, videos, and audio. The studies of qualitative nature focus on
deriving meaning from the description of the respondents. Conversely, the quantitative
methodology is designed for studies in which the goal is to examine the pattern of
variable interrelationships, as was the case in this study. The two research questions for
this study focused on examining the relationship between numerically measured variables
of patient care quality and safety. This goal informed the selection of the quantitative
design for this study.
There are three quantitative research designs that are generally used in research:
experimental, quasi-experimental, and descriptive (Rogers & Revesz, 2020). An
experimental research design was not suitable for the current study because I intended to
quantitatively investigate the relationship between variables without determining
causation or manipulating one of the variables in the study. Moreover, secondary data

36
were used in the study. Random assignment or use of an intervention or treatment was
not possible, and non-experimental study types, including descriptive designs, study the
sample in existing environments or circumstances without introducing interventions or
adjusting study conditions (Rogers & Revesz, 2020). The experimental research designs
also control extraneous variables, which was not the objective of this study. Descriptive
designs are used to describe and compare variables, while the experimental and quasi-
experimental designs are employed to predict the group’s scores and examine the
differences between them (Laerd, 2021). These designs could not be used to fill the gap
in the literature that called for exploration of a relationship between patient care quality,
patient care safety, and SES. For this reason, the differences between the two categories
of acute care hospitals were investigated without the need to manipulate any of the
variables.
Methodology
In this subsection, I provide details pertaining to the target population, sampling
procedures, and data analysis protocol that were used in the study.
Sample Selection
The selected sample comprised acute care hospitals in Illinois. I identified 20
acute care hospitals (i.e., 10 representing high-SES hospitals and 10 representing low-
SES hospitals) in Chicago, Illinois from the data accessed from the Illinois Department of
HFS. Because I used a non-probability technique to identify the study’s sample,
convenience sampling was employed. Convenience sampling allows the researcher to
subjectively identify the right sample to include in their study based on their own

37
judgment and understanding of the research questions (Stratton, 2021). Because a
nonprobability technique was used, a power analysis was not necessary, and the chosen
sample of 10 hospitals per category was used in the analysis. I selected facilities from the
Illinois Department of HFS database based on their eligibility for Medicaid’s DSH
adjustment. Acute care hospitals that met the minimum requirements to be considered
DSHs were regarded as low-SES hospitals, while those that did not meet the
requirements were considered as high-SES hospitals. Having an equal number of both
high-SES and low-SES hospitals was aligned with the study’s objectives and increased
the probability of identifying differences between the two categories of hospitals.
The hospitals used in this study were located within 50 miles of the ZIP code
62763. Data for patient care safety and quality were for the rate year 2019 (i.e., October
1, 2018 through September 30, 2019) in alignment with the hospital DSH reimbursement
data as derived from the Illinois Department of HFS (2022) database (Illinois Department
of HFS, 2022). As stated before, I noted the assumptions and delimitations of the study to
avoid diverging from the purpose and topic of research. The data collected by the IDPH
are accessible to the general public, and were, therefore, assumed to be free of errors.
IDPH has provided a compendium of health care facilities in Illinois and their Medicaid
reimbursement data with detailed explanations on the eligibility of each facility for
DSH’s payments (Illinois Department of HFS, 2020). The data provide aggregated
measures of Medicaid inpatient utilization rates, total Medicaid inpatient days, and the
total hospital inpatient days, which were used to determine the eligibility of acute care
hospital for DSH, MHVA, and MPA.

38
Sampling Procedure
Sampling entails using a representative set of the population to find an estimate of
the characteristics for the whole population (Singh & Masuku, 2014). For a large
population, sampling is both efficient and saves on the time necessary for conducting
research. Units of study can either be randomly or conveniently sampled; however, the
sampling procedure must take into consideration the cost of doing the data collection as
well as the reliability of the data for drawing inferences about the population of the
sample (Singh & Masuku, 2014). A sample allows for a detailed and accurate analysis of
the data (Taherdoost, 2016). In this study, I used convenience sampling to identify the 20
acute care hospital participants within Illinois: 10 hospitals that predominantly serve
high-SES patients and 10 hospitals that mainly serve low-SES patients. An equal number
of low-SES and high-SES hospitals were included to increase the probability of
identifying actual differences between hospital categories.
Operationalization and Instrumentation
The alternate exception method permits eligible hospitals to receive up to 30% of
net inpatient revenue from CMS as an adjustment for the cost of indigent care (MLN,
2021). Certain hospitals serve a disproportionately high number of low-income patients,
and such hospitals are often located in urban areas, have at least 100 beds, and more than
30% of their net inpatient revenue is funded by state and local government sources for
indigent care (MLN, 2021). The Illinois Department of HFS database provides a data set
on hospitals’ reimbursement and Medicare adjustment for the year 2020. Using the DSH

39
designation of hospitals by CMS, I identified 10 Medicare DSH and 10 non-Medicare
DSH hospitals from the data set to use as participants in this study.
For each of the 20 hospitals, quality and safety data was taken from IDPH,
through its link to safety and quality of patient care (CMS, 2022). The Illinois Hospital
Report Card and Consumer Guide to Health Care provides information on quality and
safety of patient care for various hospitals in Illinois (CMS, 2021). The quality of patient
care was determined using readmission rates. Patient care safety statistics was provided
by the rate of HAIs observed in the identified acute care hospitals. Average scores of
patient care quality and patient care safety in low SES and high SES hospitals were
determined and compared using the independent sample t test.
Data Analysis Plan
I imported the data gathered in this study in SPSS v26.0. The data was cleaned to
affirm the accuracy of the variables and indicators as reported in it. Descriptive statistics
such as the mean, standard deviation, and range values were used to describe the
variables of the study. To test the hypotheses posed in the study, two independent
samples t tests analyses were conducted. For the first hypothesis, patient care quality was
compared between low SES and high SES acute care hospitals to determine if significant
difference existed between them. In the second hypothesis, patient care safety between
low SES hospitals and high SES hospitals was compared to determine if a statistically
significant difference existed. The alpha level, p = 0.05, was used for the two analyses. A
p value lower than .05 implied that null hypothesis was rejected and upheld existence of
differences in patient care quality and safety of care between low SES and high SES

40
acute care hospitals. Conversely, the null hypothesis was not rejected when the p value
exceeded .05 as this implied that there was no statistically significant association
between: (a) hospitals’ SES and patient care quality, and (b) hospitals’ SES and patient
care safety.
Threats to Validity
External validity refers to the generalizability of the results while internal validity
refers to the extent to which what was done in the study produced the expected results
and that the results were not influenced by other factors (Price et al., 2017). In this
subsection, I discuss threats to the external and internal validity of the study.
Selection bias has one of the most profound effects on a study’s external validity
since the way in which samples were chosen influence how generalizable the findings are
from the samples to the rest of the population (Liu et al., 2019). In quantitative research,
the sample taken should ideally be representative of the larger population to maximize
the generalizability of the findings. Liu et al. (2019) opined that random (probability)
sampling can be used to reduce the presence of selection bias since all the samples are
drawn at random. In other words, because each sample is equally as likely to be chosen,
the results are more likely to be more generalizable to the rest of the population (and
potentially to other populations) than they would have been had the samples been chosen
purposefully or for convenience. When the sampling strategy does not result in a
representative sample of participants, as can be the case when purposive sampling is
used, it is important to consider how this might influence the generalizability of the
results. It is important to note that the study’s findings are only generalizable to the target

41
population, and that the specific characteristics that define the target population make it
difficult to apply these results to other groups.
Internal validity refers to the extent to which the research design supports the
conclusions made (Price et al., 2017). Non experimental designs, like the one used in this
study, typically have lower validity than other quantitative research designs because the
variables are not manipulated or controlled (see Price et al., 2017). This means that it is
more likely that an unmeasured variable, called a confounding variable, influenced the
study’s results. An example of a confounding variable in the context of this study would
be the influence of provider’s age and experience on patient care quality and safety.
Other potential threats to the internal validity of the study include changes in
instrumentation, participant selection, maturation, and the administration of multiple tests
(Rahman, 2020). The use of secondary data sourced from existing reports, instead of
primary data collected during interviews or from surveys, increased this study’s internal
validity. The data were not influenced by patients’ perceptions of the study, the number
of administered tests, or the data collection methods used.
Ethical Procedures
Ethical considerations constitute a key component of the research process and
were considered throughout the design and implementation of this study (Liu et al.,
2019). Getting approval from the university’s Institutional Review Board was the first
step taken to address any ethical concerns that could have risen from this study. Thus, I
submitted my Institutional Review Board request and received the approval number 08-
30-22-0745003.

42
Issues such as confidentiality and anonymity were continuously renegotiated.
With regard to that, I collected secondary from the IDPH concerning the quality of
patient care and patient care safety and associated SES. The data considered in the study
did not include identifiable information, while all the data gathered for the study was
accessible only to the researcher. Furthermore, the data was only used for the purpose of
this study. An informed consent form was also unnecessary because no primary data were
collected. All the collected data were locked and stored in file cabinets and password
protected computer files for three years; thereafter, all information related to the study
will be destroyed and permanently deleted.
Summary
In this section, I presented the research employed in the study and discussed the
procedures for data analysis and concerns relating to the study’s validity and ethical
procedures. To examine potential relationships between variables, I conducted
independent samples t test analysis. This statistical test is appropriate for this study
because it is useful in determining if any significant differences exist in the mean values
of any two given groups of data. Potential validity threats included selection bias and
confounding variables. I did follow all ethical procedures as required by the university’s
IRB.
In Section 3, I present the outcomes of data collection, descriptive statistics,
independent samples t test, and logistic regression model. I used the logistic regression
model to determine the strength of association between independent variable and the
dependent variables.

43
Section 3: Presentation of the Results and Findings
Introduction
The purpose of this quantitative study was to examine if patient care quality and
safety are related to hospitals’ SES among Chicago’s acute care hospitals. The study
involved three variables: The independent variable was hospitals’ SES, while the
dependent variables were patient care quality and safety provided by the acute care
hospitals. I determined the SES of acute care hospitals using the Medicare DSH
designation whereby low-SES hospitals are those eligible for Medicare DSH payment
adjustments while high-SES hospitals do not qualify for DSH payments under the
formula applied by the CMS. I performed statistical analysis of the data to provide
important information to help in designing models that enhance the provision of safe and
quality patient care for diverse urban populations in Illinois. The results may also inform
positive social change in acute care hospitals in Chicago by articulating how the variables
of the study relate to inform patient care quality and safety.
In this section, I provide the time frame for data collection, the results of the
analysis, and an interpretation of the findings. A discussion of the study’s limitations, my
recommendations for future research, an explanation of the implications for positive
social change, and a conclusion follow. This study was guided by the following two
research questions:
RQ1: Is there a difference in patient care quality between hospitals of low SES
and hospitals of high SES among Chicago’s acute care hospitals?

44
RQ2: Is there a difference in patient care safety between hospitals of low SES and
hospitals of high SES among Chicago’s acute care hospitals?
Data Collection
I obtained the secondary data used to conduct this study from the IDPH. The
sample used in the study comprised 20 acute care hospitals in Chicago, Illinois (i.e., 10
representing high-SES hospitals and 10 representing low-SES hospitals) and were
accessed through the Illinois Department of HFS database. The Illinois Department of
HFS database provides the eligibility status of each acute care hospital in Illinois for
Medicaid’s DSH payments and processes the list of hospitals eligible for DSH, MPA, and
MHVA every year. The data used for this study were for the rate year of 2019 (i.e.,
October 2018 through September 2019).
Patient care safety and patient care quality data were derived from the IDPH’s
Division of patient safety and quality. As outlined in Section 2 of this study, I analyzed
patient care safety and quality data using proxy indicators. Patient care safety was
determined using HAIs, while patient care quality was determined using hospital
readmission rates. The data from the IDPH’s Division of patient safety and quality
indicated the readmission rates for each hospital for three conditions: pneumonia, heart
failure, and heart attack. The average value of the three measures was computed to have
one value that represented the hospital’s readmission rate. Where values were indicated
as not applicable, I assumed that the indicated measures represented the average
hospital’s readmission rate.

45
Hospitals reported different diseases associated with HAIs. I closely analyzed the
data for HAIs and removed conditions with missing values or whose values were
indicated as not applicable. This then left the data with two conditions associated with
HAIs: clostridium difficile infections and central-line associated bloodstream infections. I
compared the observed values of the two conditions across the 20 acute care hospitals
and found that the central-line associated bloodstream infections data were not
statistically significant in the study because most hospitals recorded zero observed events
(see Table 1). Although the numerical data presented in Table 1 are accurate, the names
of the study sites are pseudonyms in tandem with the university’s participant protection
policy. The clostridium difficile infections data were assumed to represent the measure of
HAIs across all acute care hospitals used in the study.
Table 1
Measure of HAIs at Each Acute Care Hospital
Hospitals CDI
CLABSI
St. Luke’s Hospital 42
1
McLurie ABC Hospital 55
5
XY Regional Hospital 6
0
Pattz Regional Medical 5
0
St. Mark Hospital 17
3
Petersburg Medical Center 12
0
Sinai Medical Center 36
2
McHoughton Children’s Hospital 53
0
Friends of Purpose Medical 37
3
H Alexian Sisters Medical 37
1
St. Mason Hospital 0
0
Capitol Memorial Hospital 2
0
Finich-American Hospital 5
0
Torongo District Hospital 181
5

46
Halprezy District Hospital 2
0
DGT Memorial Hospital 11
0
Palmharst Hospital 20
4
St. Edward’s Hospital 66
0
Presence St. John Medical 14
0
Gateway Community Hospital 96
0
Note. CDI = clostridium difficile infections, CLABSI = central-line associated
bloodstream infections. Adapted from “State Reports of Current Interest” by the Illinois
Department of Public Health, 2019,
(http://www.healthcarereportcard.illinois.gov/contents/view/State_Reports_of_Current_I
nterest)
Results
Descriptive Statistics
HAIs
I used HAIs as a proxy of patient care safety. The descriptive analysis of the HAIs
was carried out to assess their distribution across high- and low-SES acute care hospitals.
The five observable cases of HAIs that were captured in the high-SES acute care
hospitals had a mean of 64.4, as shown in Figure 1, while the seven observable cases
captured in the low-SES acute care hospitals had a mean of 30.86 (see Figure 2). These
results indicate that the high-SES hospitals experienced higher incidences of HAIs than
the low-SES hospitals; therefore, there is a higher likelihood of compromising patient
care safety in high-SES hospitals than in the low-SES hospitals.
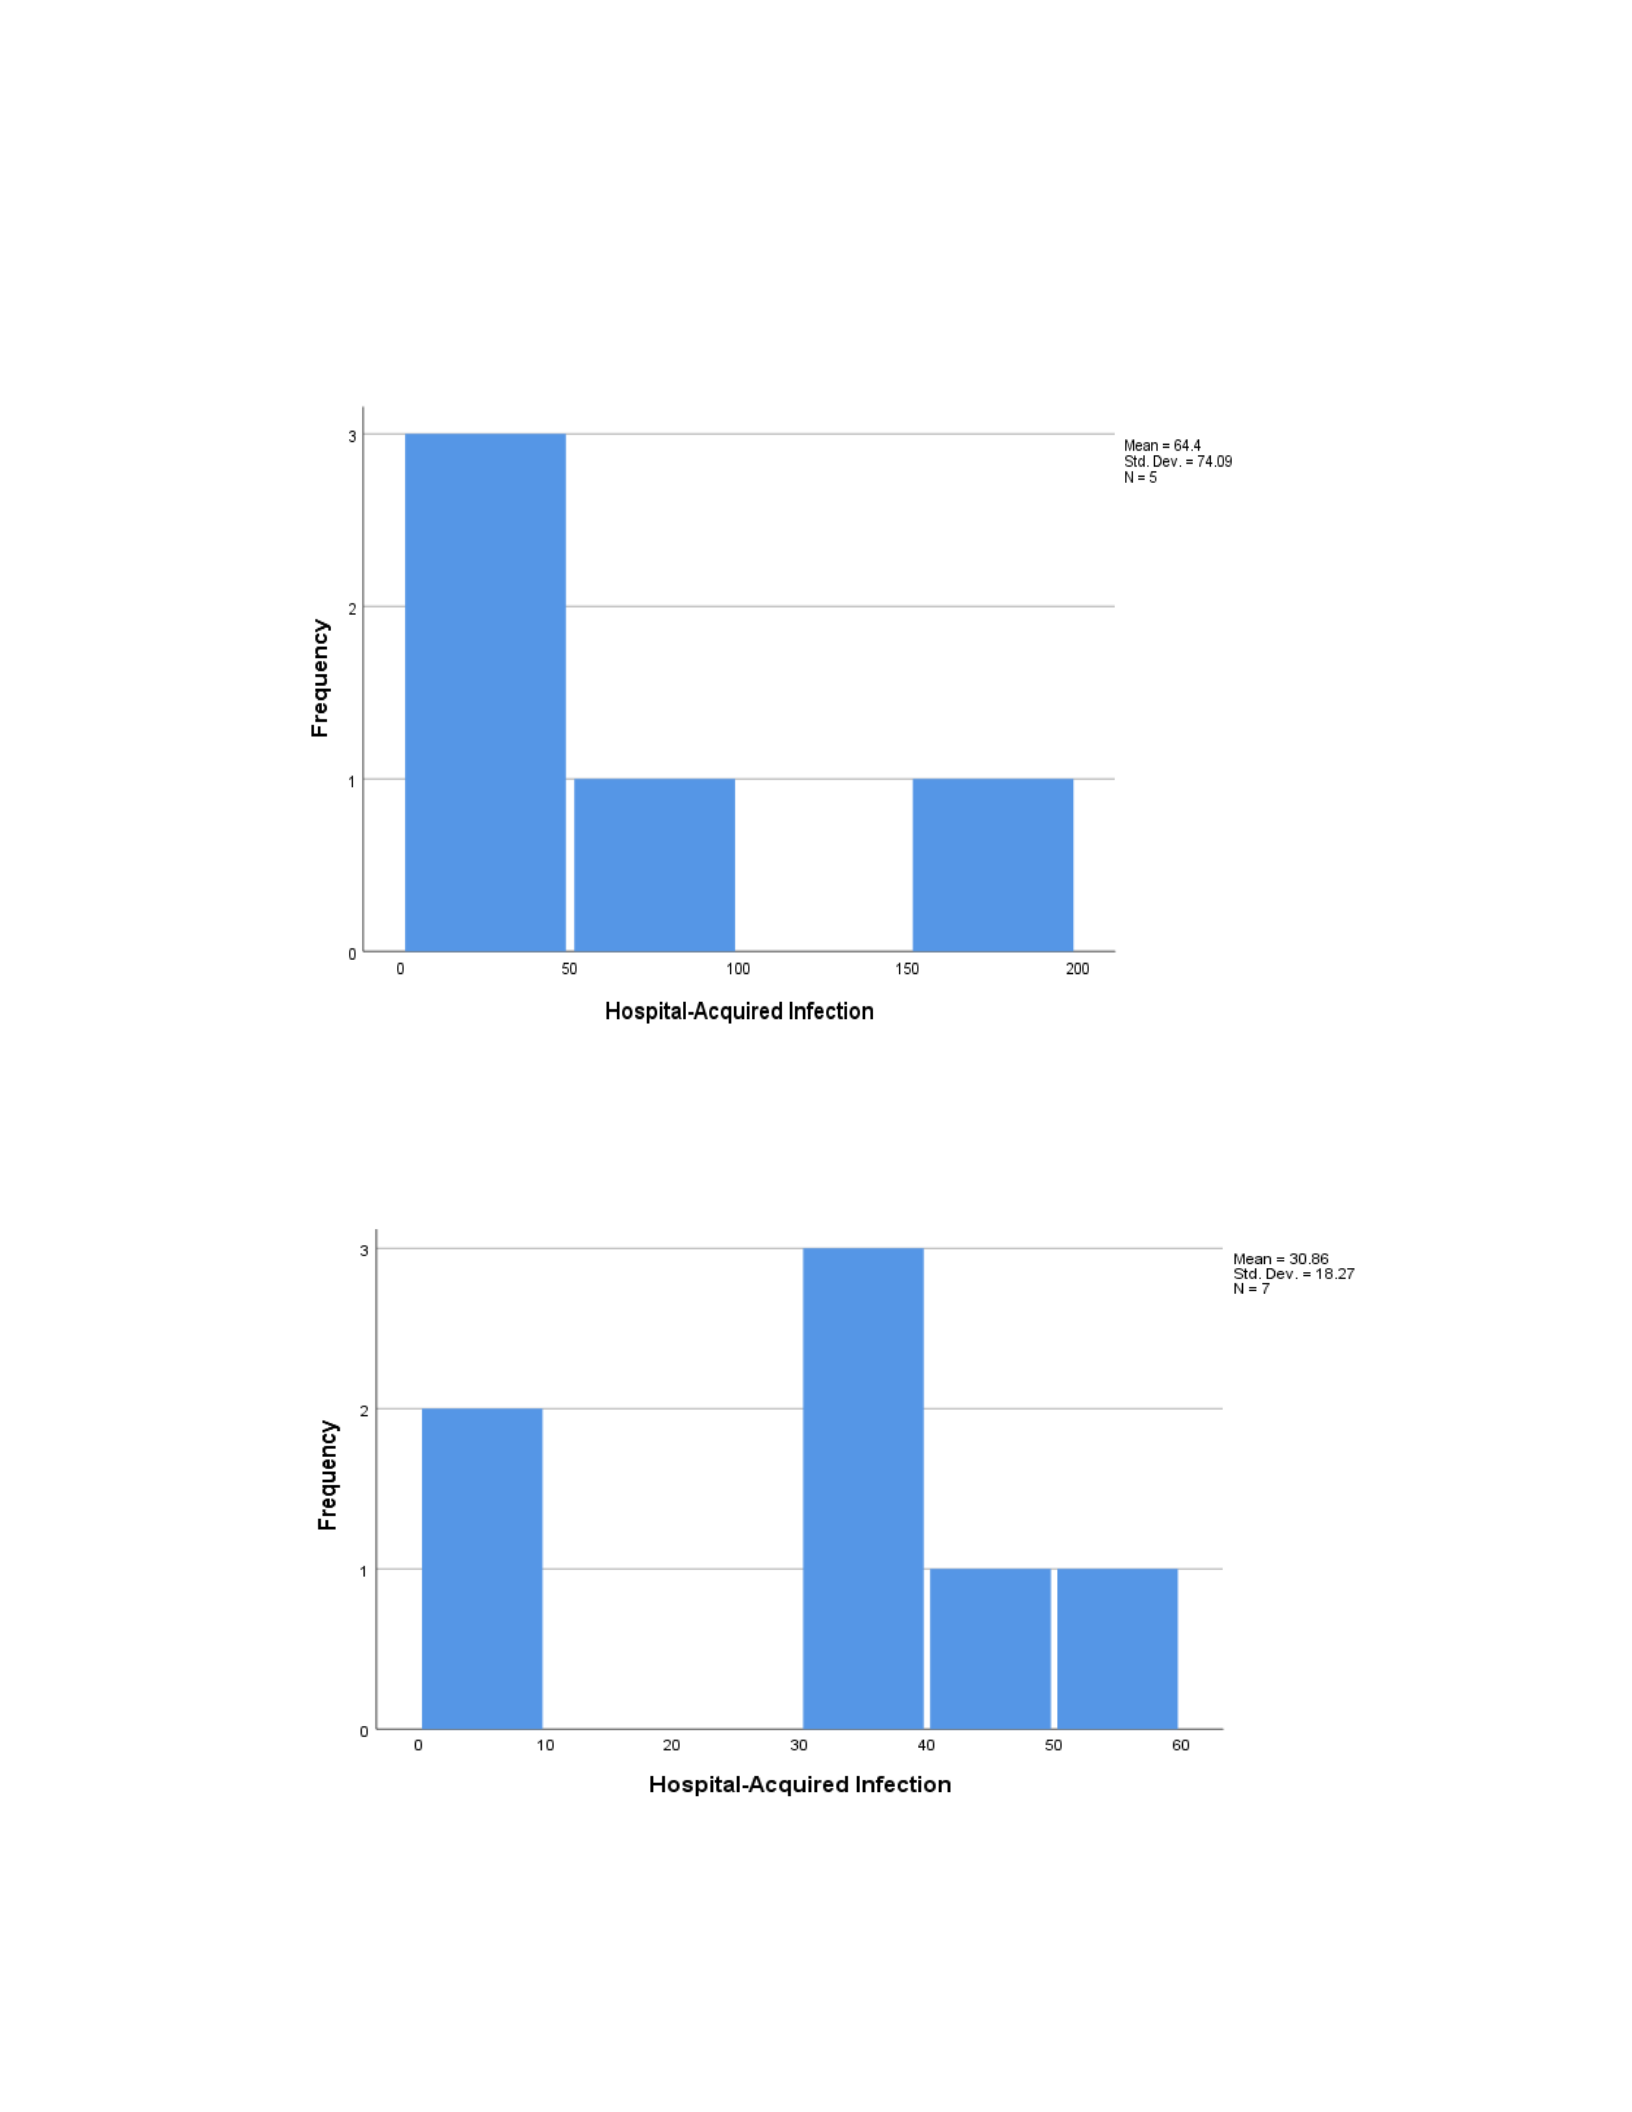
47
Figure 1
Frequency of HAIs in High-SES Hospitals
Figure 2
Frequency of HAIs in Low-SES Hospitals
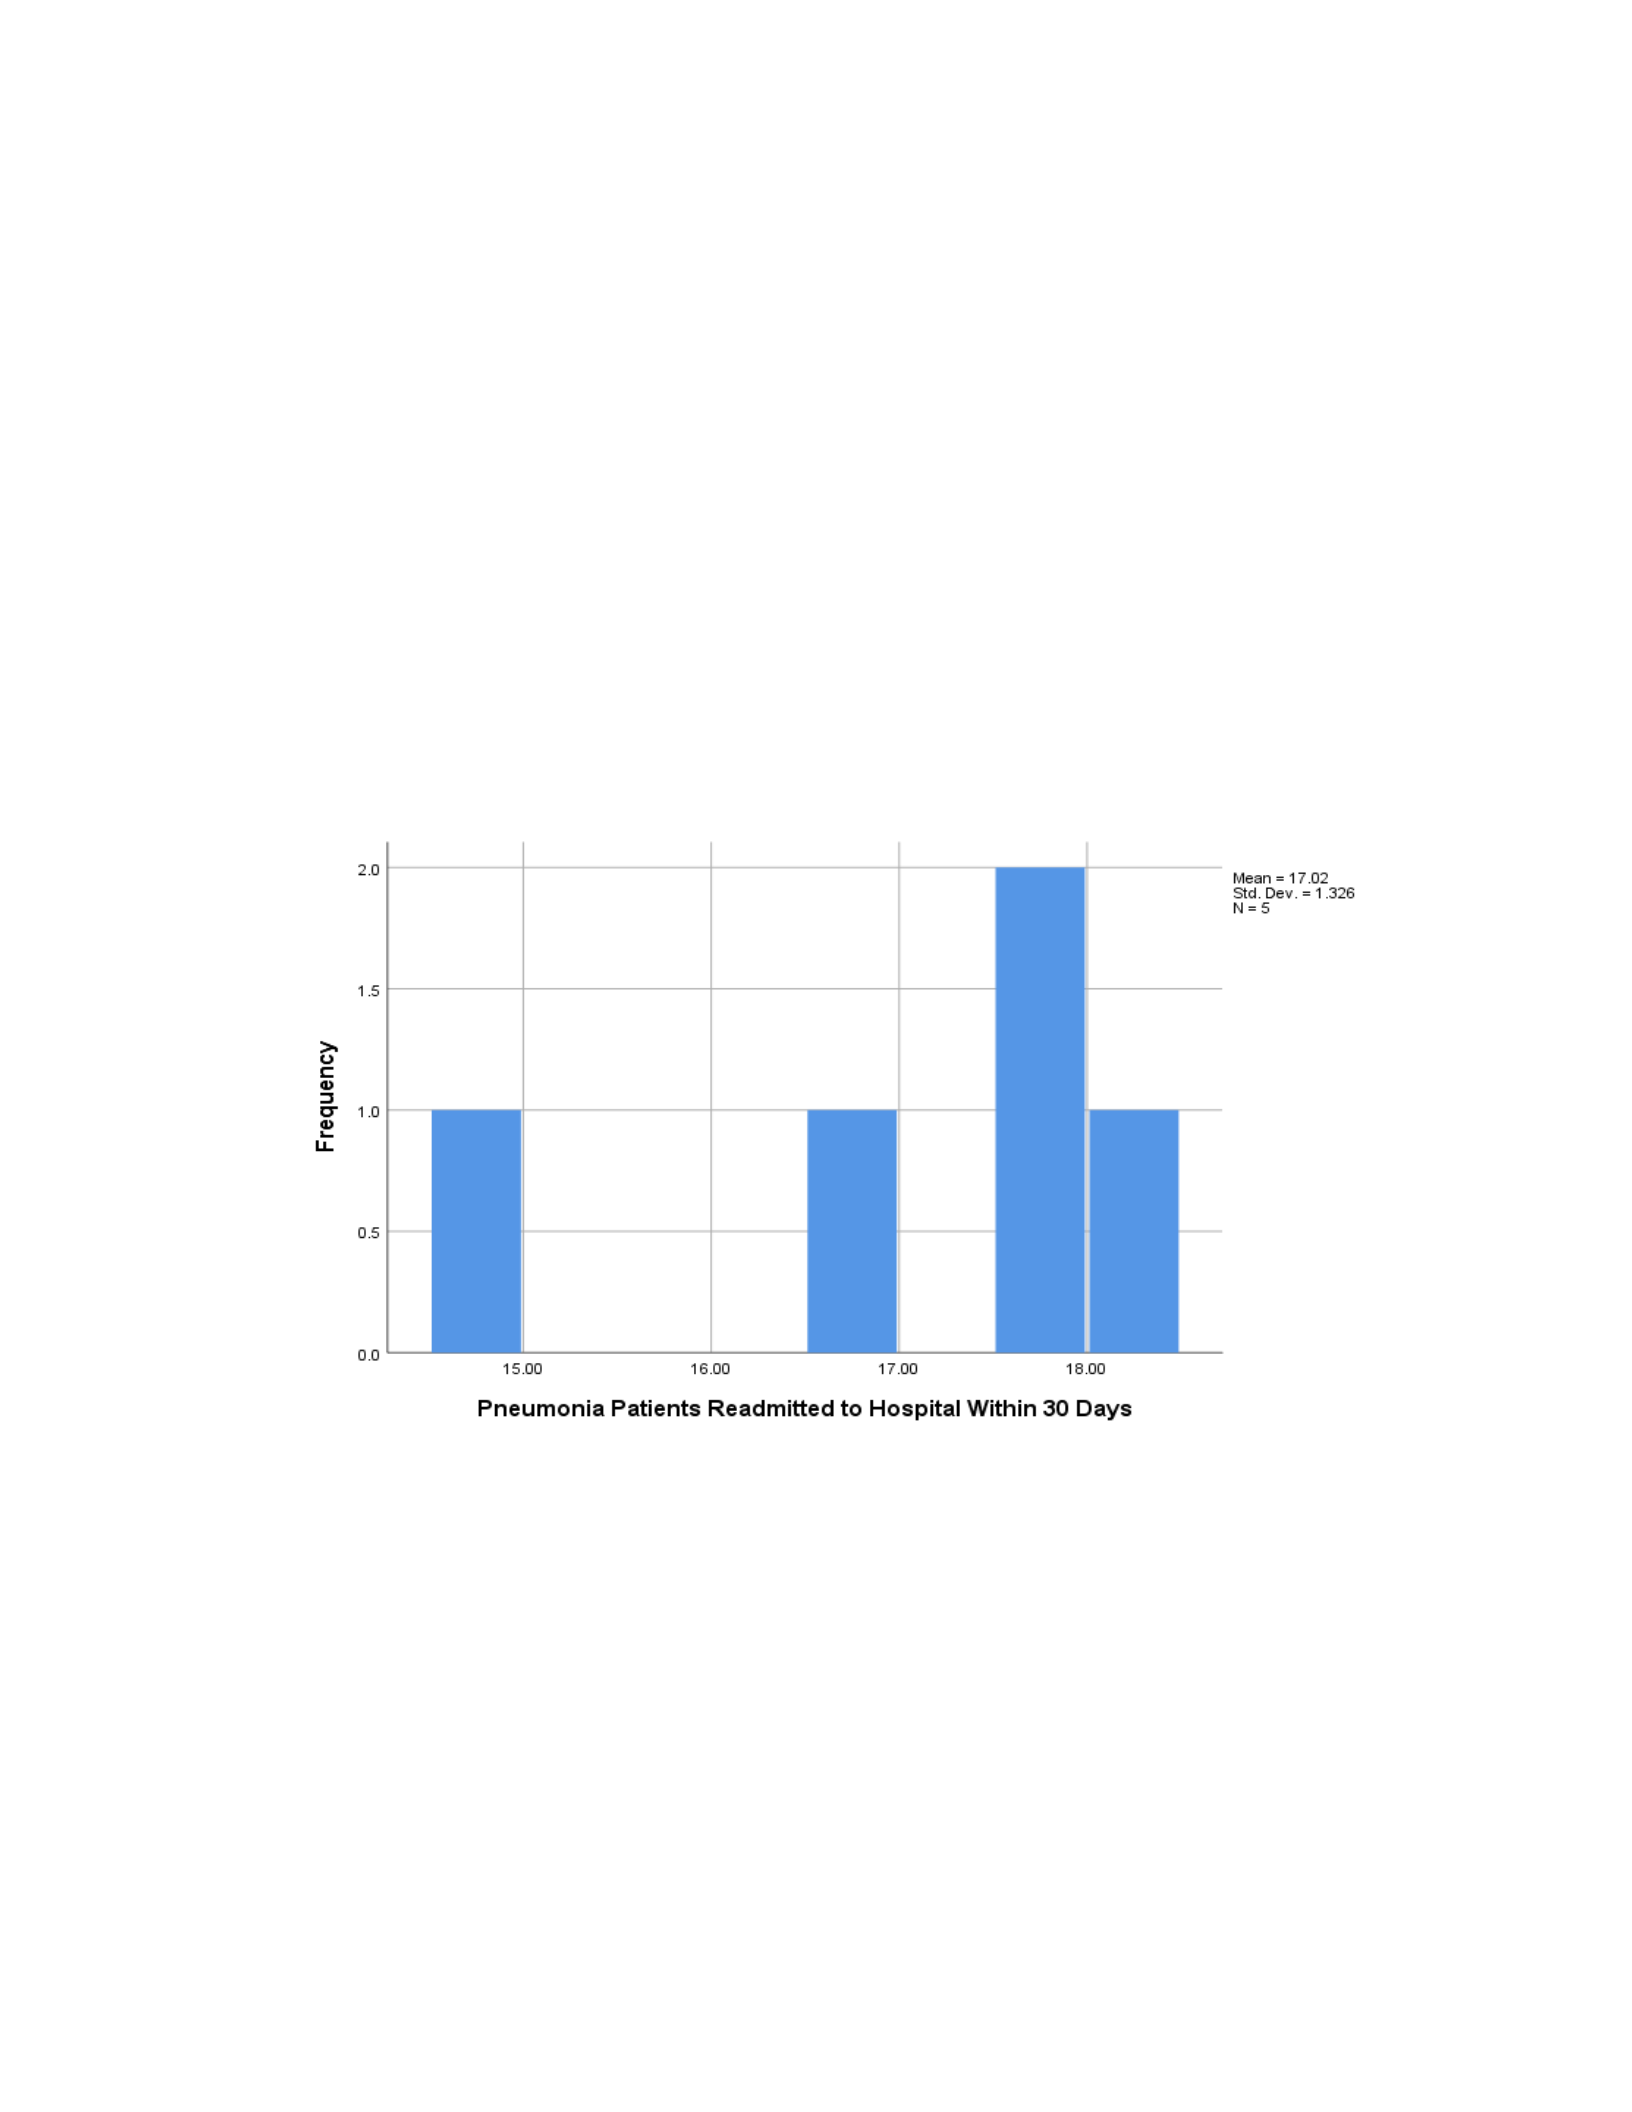
48
Hospital Readmission Rates
I used the average of readmission rates for pneumonia patients, heart failure
patients, and heart attack patients within 30 days as a proxy factor for patient care quality.
The descriptive analysis of the readmission rates for each of the elements is outlined in
Figures 3–8.
Readmission Rates of Pneumonia Patients.
Figure 3
Frequency of Pneumonia Readmissions in High-SES Hospitals
The five observable cases in readmission numbers for pneumonia patients in the
high-SES acute care hospitals had a mean of 17.02, as shown in Figure 3. Figure 4 shows
seven cases of readmissions for pneumonia patients in the low-SES acute care hospitals,
with a mean of 16.81. The results indicate that high-SES hospitals experienced higher
incidences of readmission for pneumonia patients within 30 days of the period of analysis
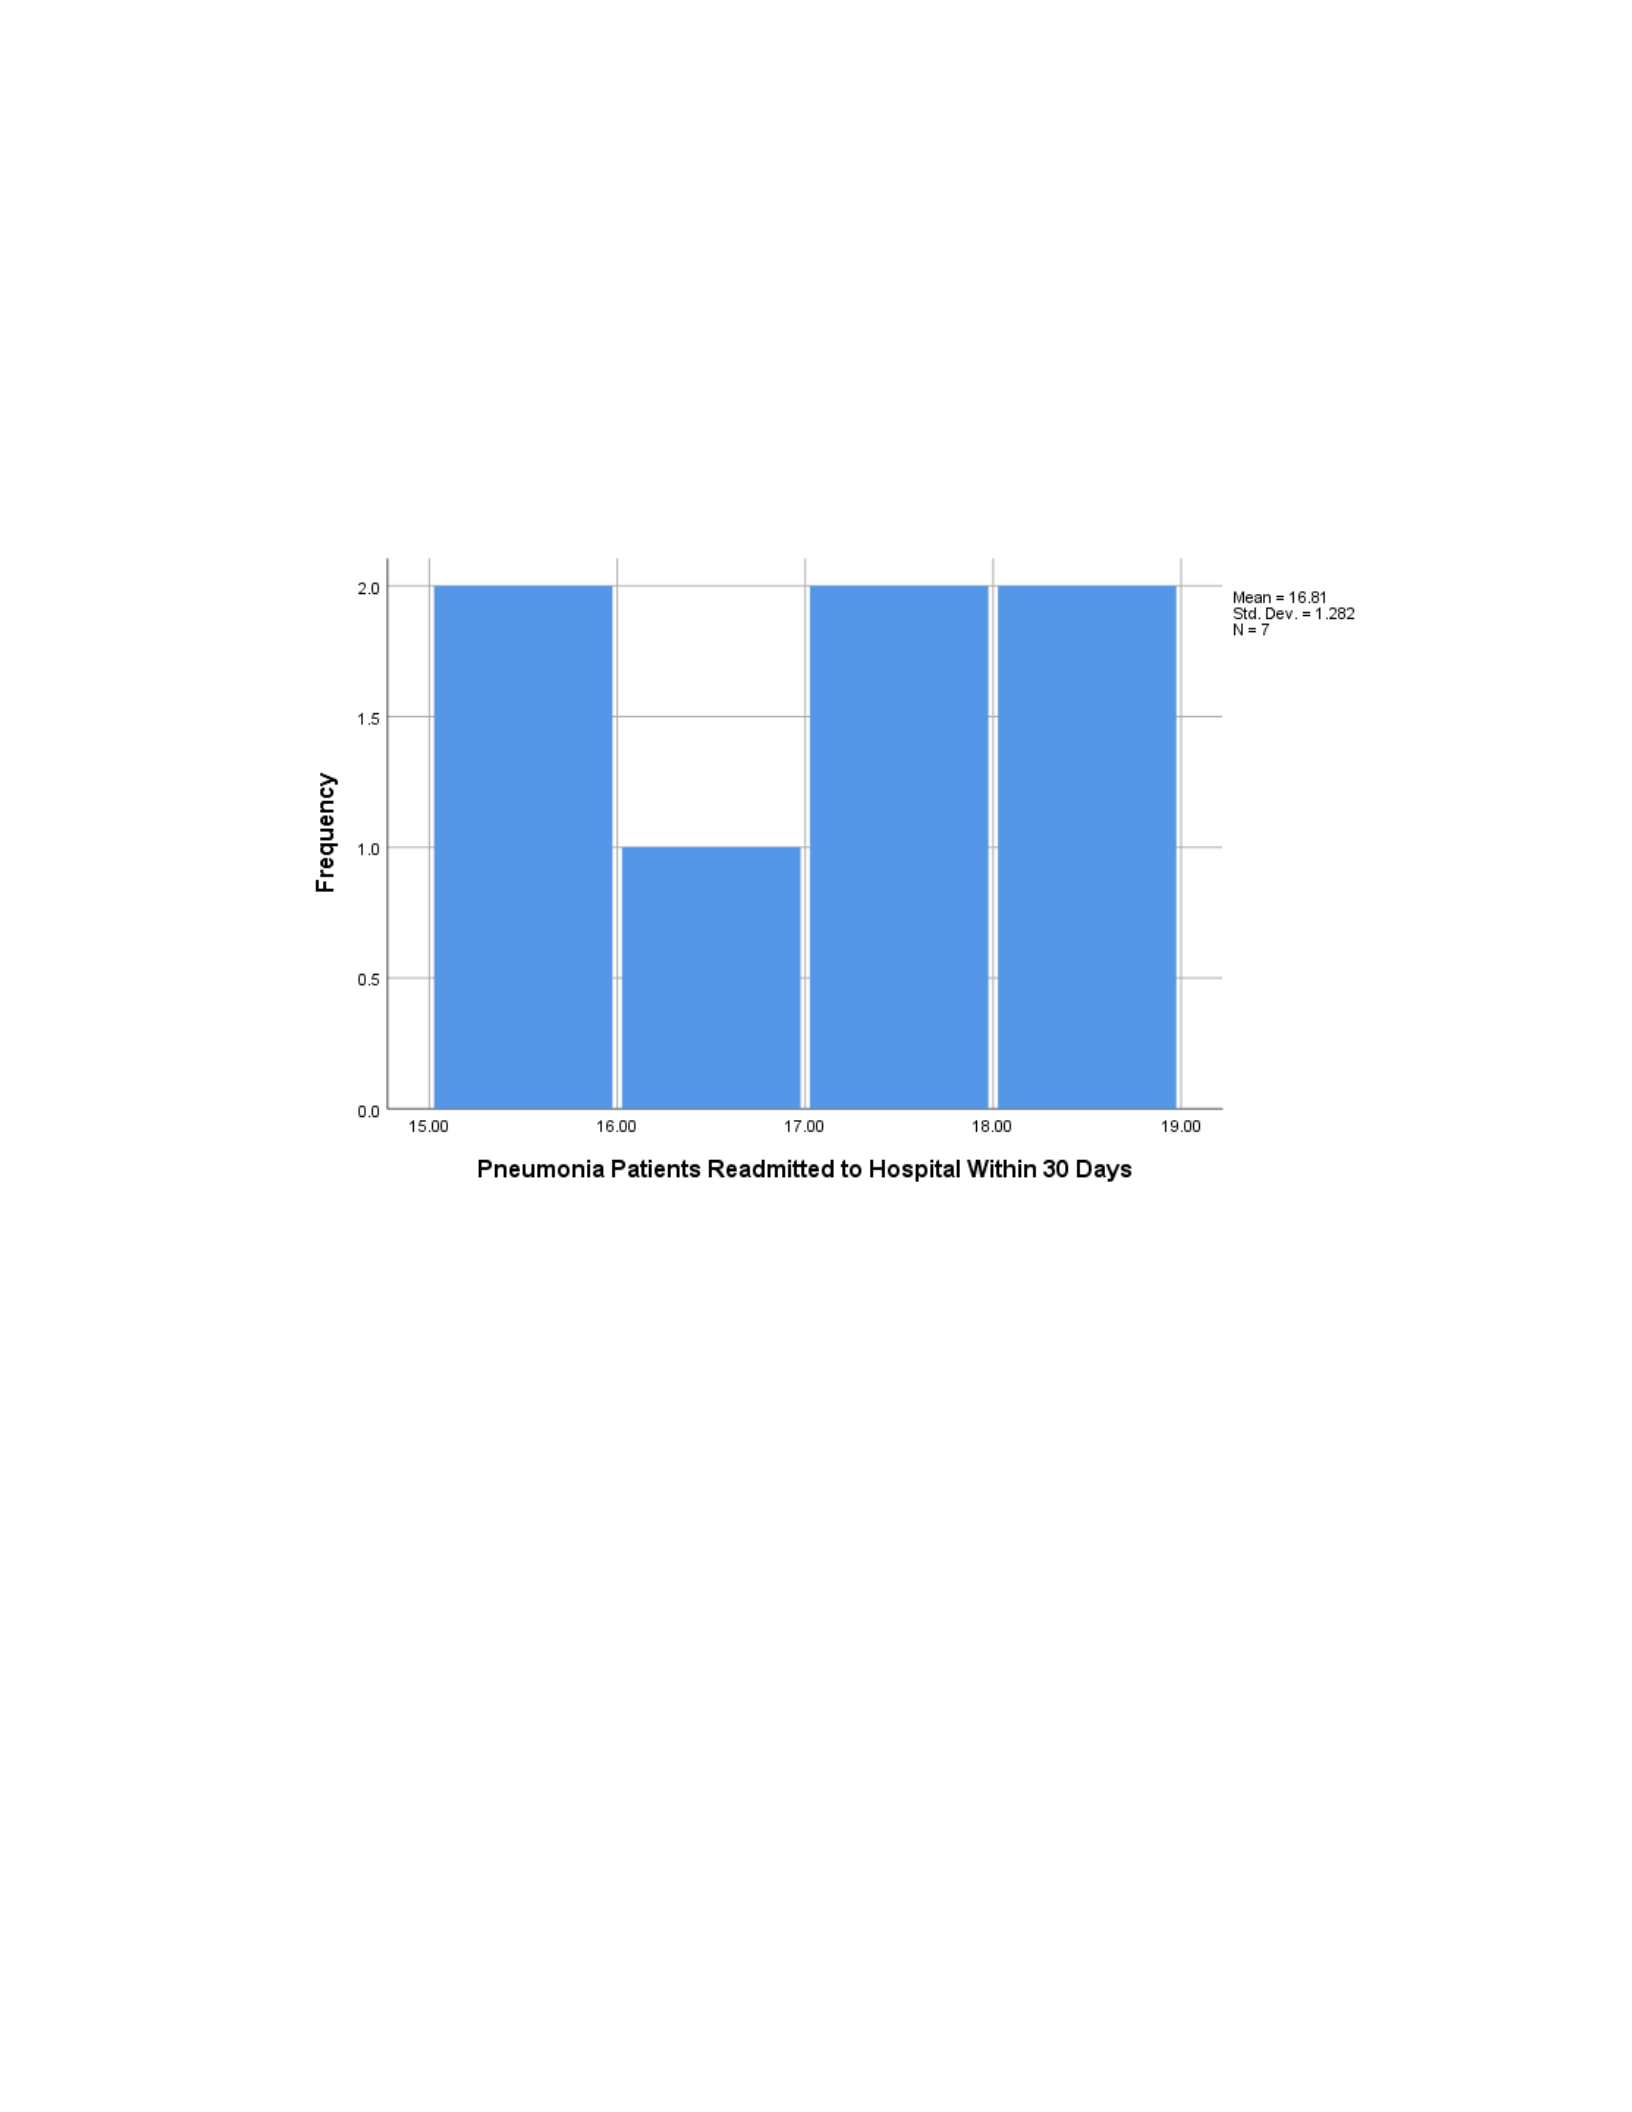
49
than the low-SES hospitals and, therefore, have a higher likelihood of compromising
patient care quality.
Figure 4
Frequency of Pneumonia Readmissions in Low-SES Hospitals
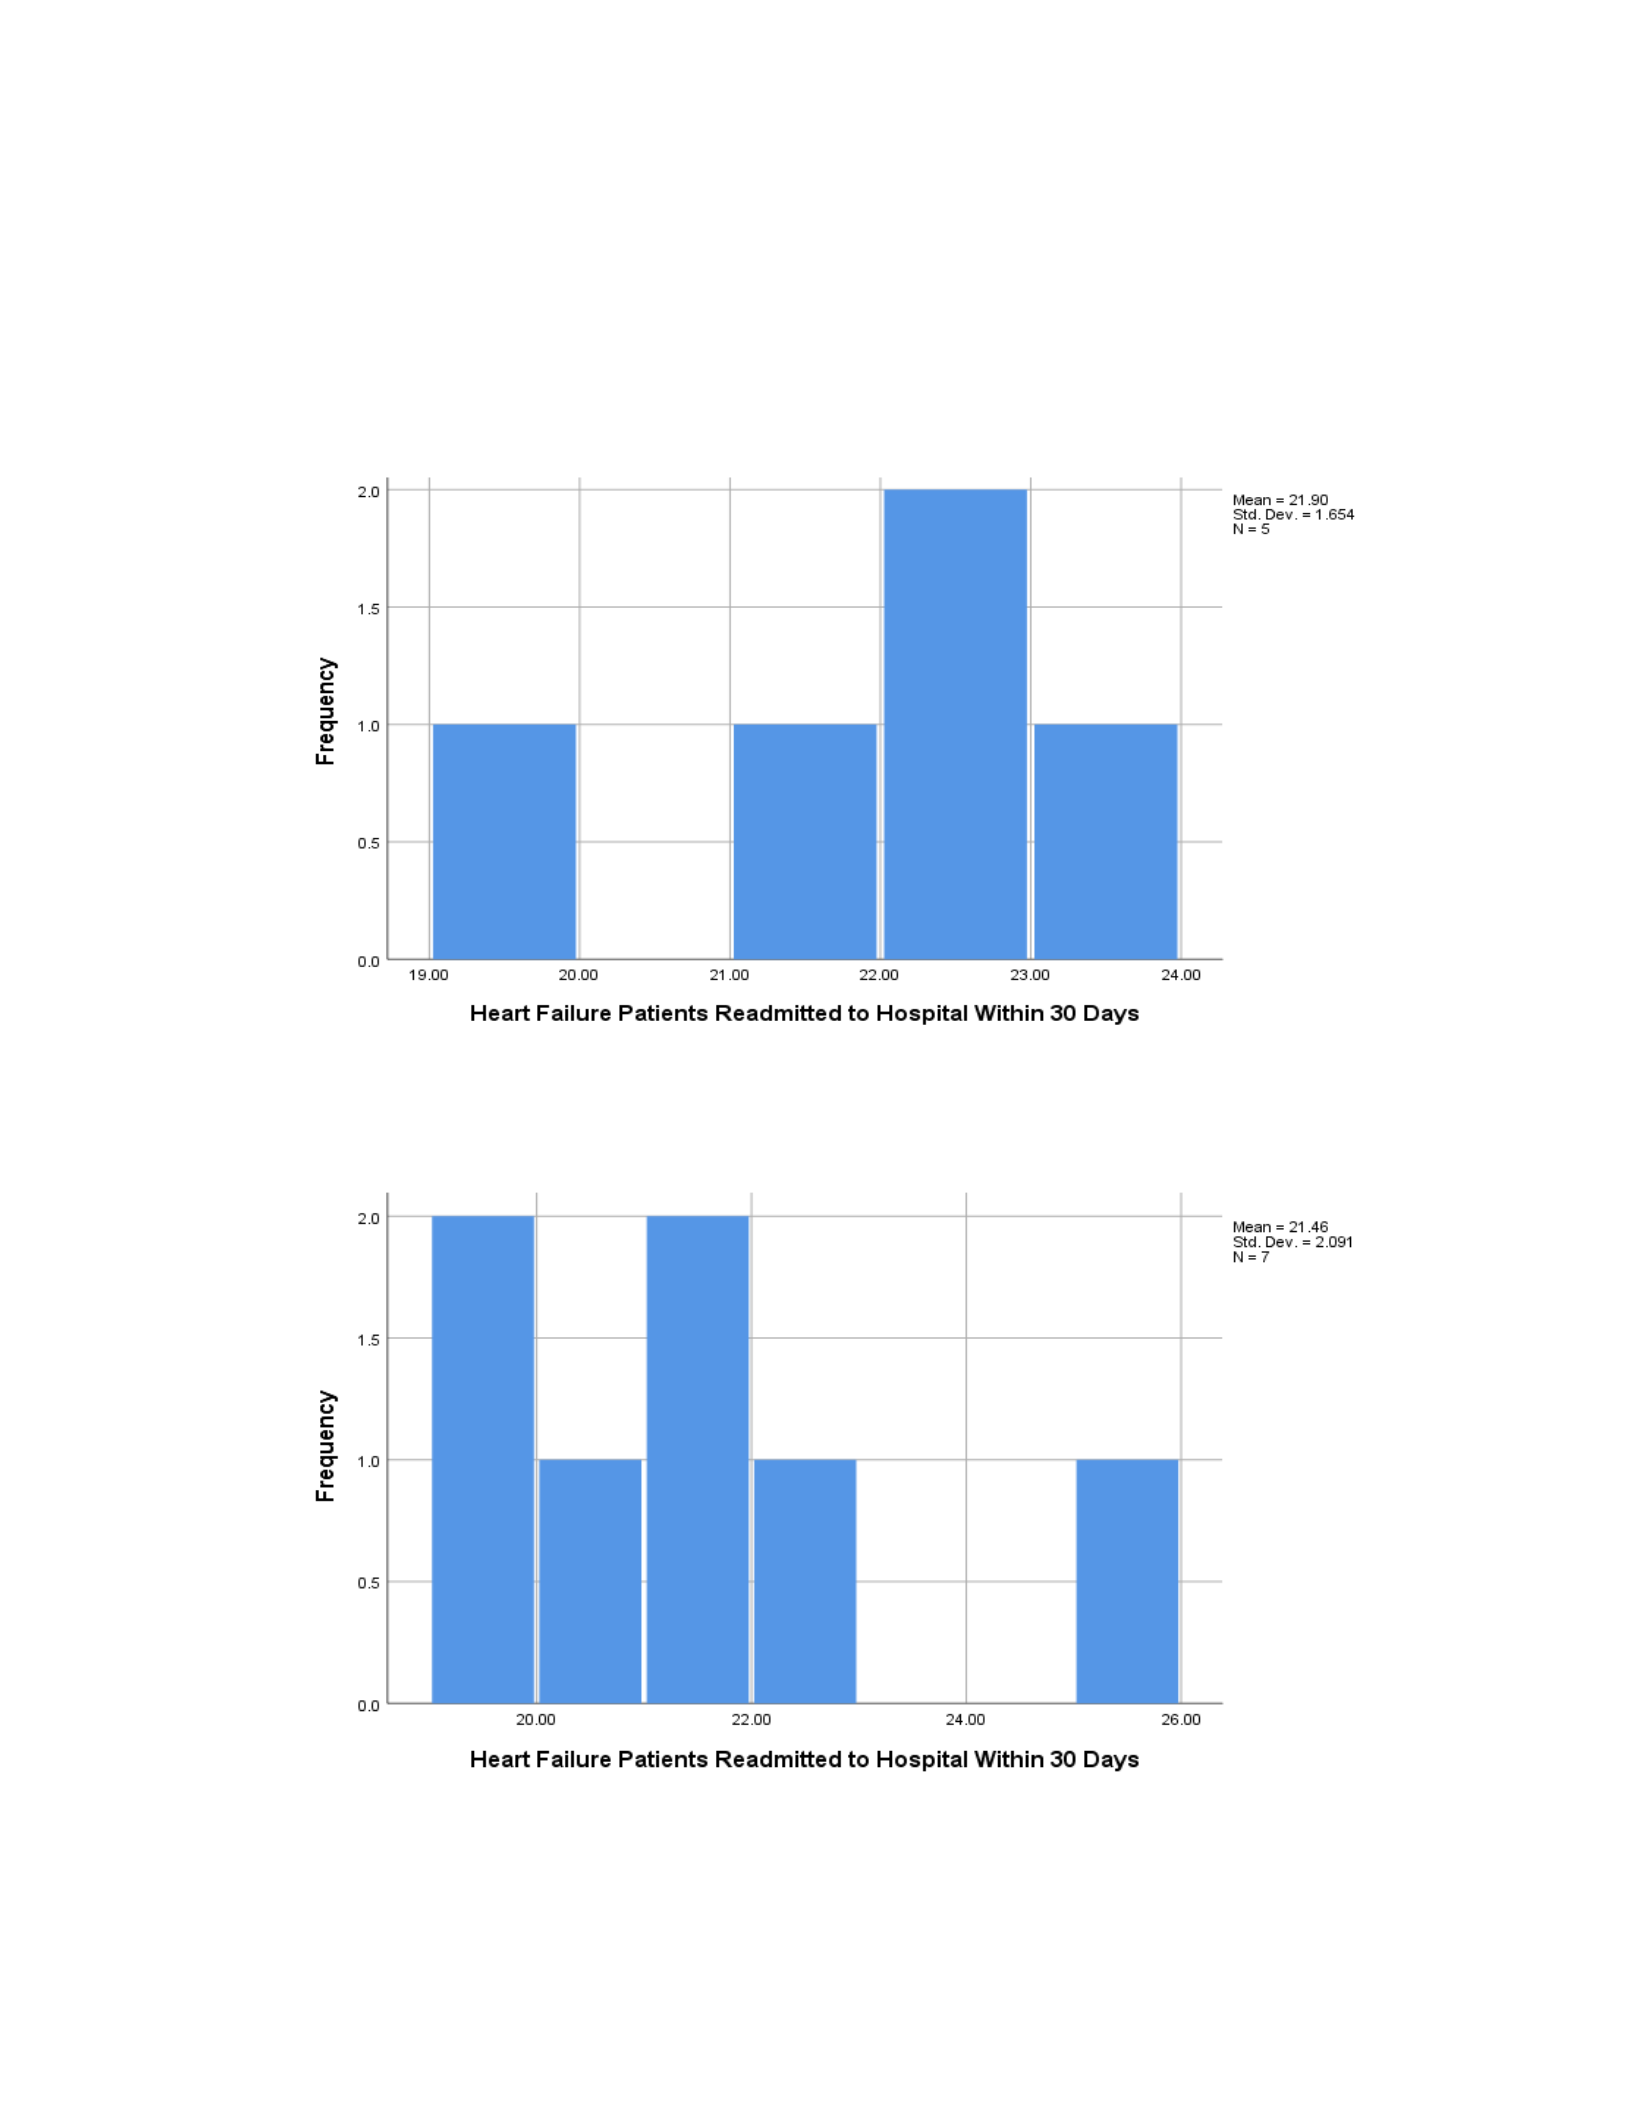
50
Heart Failure Patients.
Figure 5
Frequency of Heart Failure Readmissions in High-SES Hospitals
Figure 6
Frequency of Heart Failure Readmissions in Low-SES Hospitals

51
The observable cases of the readmissions of heart failure patients in high-SES
acute care hospitals had a mean of 21.90 (see Figure 5), while readmissions in low-SES
acute care hospitals had a mean of 21.46, as shown in Figure 6. According to the results,
high-SES hospitals experienced higher incidences of patients being readmitted for heart
failure than low-SES hospitals. The implication is that high-SES acute care hospitals
have a higher likelihood of compromising patient care quality compared to low-SES
hospitals
Heart Attack Patients. For the cases observed, the mean of the readmission rates
of heart attack patients in high-SES acute care hospitals was 16.46 (see Figure 7). The
readmissions for heart attack patients in low-SES acute care hospitals had a mean of
16.50, as shown in Figure 8. These results were an exception because the low-SES
hospitals experienced higher incidences of patients being readmitted for heart attack than
the high-SES hospitals, unlike the other assessed ailments (i.e., pneumonia and heart
failure).
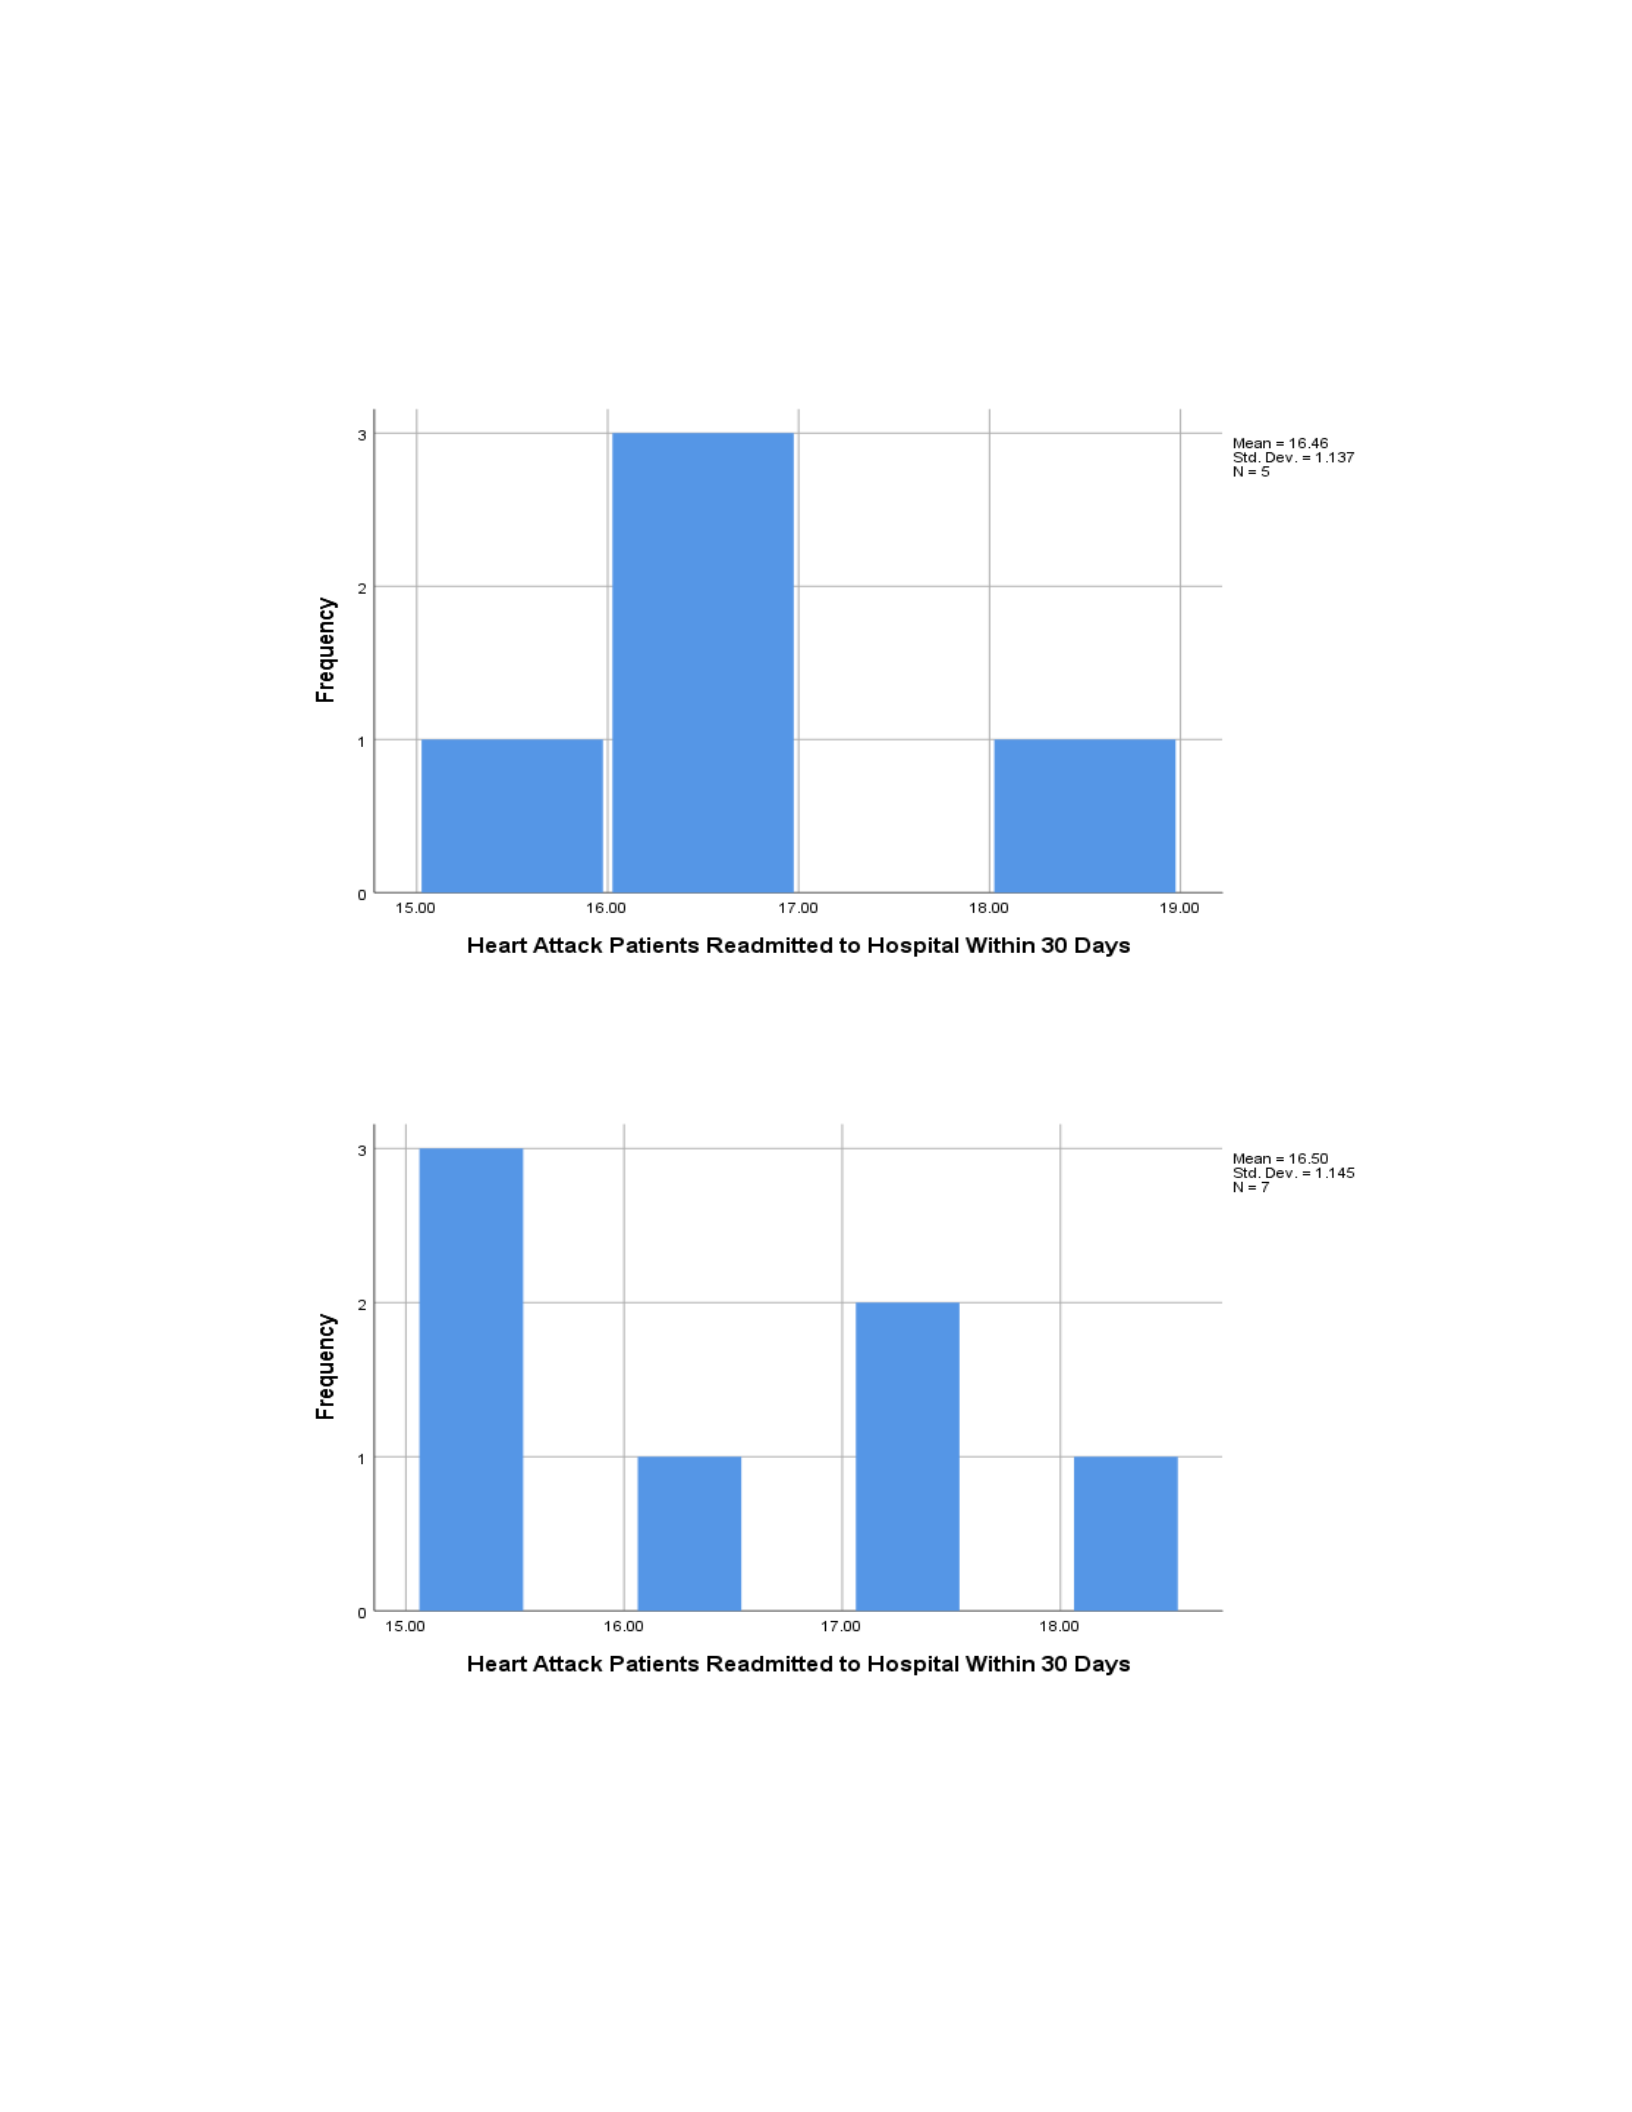
52
Figure 7
Frequency of Heart Attack Readmissions in High-SES Hospitals
Figure 8
Frequency of Heart Attack Readmissions in Low-SES Hospitals

53
Research Question 1: Patient Care Quality and Hospital SES
Independent samples t test was conducted to compare the quality of patient care
between low SES and high SES acute care hospitals in Chicago. The outcome of the
group statistics comparing patient care quality with hospitals’ SES revealed low
association between the two variables. Table 2 shows that patient care quality is not
significantly different between low SES hospitals (M = 18.49, SD = .9400) and high SES
hospitals (M = 18.32, SD = 1.6138).
Hypothesis Testing
Table 3 shows that there is no statistical significant difference in patient care
quality between low SES hospitals and high SES hospitals, p = .787 (p ≤ 0.05). The null
hypothesis was not rejected and the alternative hypothesis was rejected. The outcome
implies that patient care quality was not dependent on the hospitals’ socio-economic
status.
Research Question 2: Patient Care Safety and Hospital SES
Independent samples t test was conducted to compare patient care safety between
the low SES and high SES acute care hospitals in Chicago. Table 2 shows group statistics
analysis in high SES hospitals (M = 39.70, SD = 58.994) and low SES acute care
hospitals (M = 30.0, SD = 18.637), stating that the two variables of patient care safety and
hospitals’ SES had low association.
Table 2
Group Statistics Analysis
Hospital Socio-Economic
Status (SES) N
Mean
Std.
Deviation
Std. Error
Mean

54
Patient care
safety
High socio-economic status 10
39.70 58.994 18.655
Low socio-economic status 10
30.00 18.637 5.893
Patient care
quality
High socio-economic status 10
18.3200
1.61379 .51032
Low socio-economic status 9 18.4889
.94004 .31335
Hypothesis Testing
From the outcome shown in Table 3, there is no statistically significant
association between hospital’s SES and patient care safety p = .626 (p ≤ 0.05). Therefore,
the null hypothesis was not rejected; rather, the alternative hypothesis was rejected. The
outcome implied that the patient care safety was not dependent on the hospital’s SES.
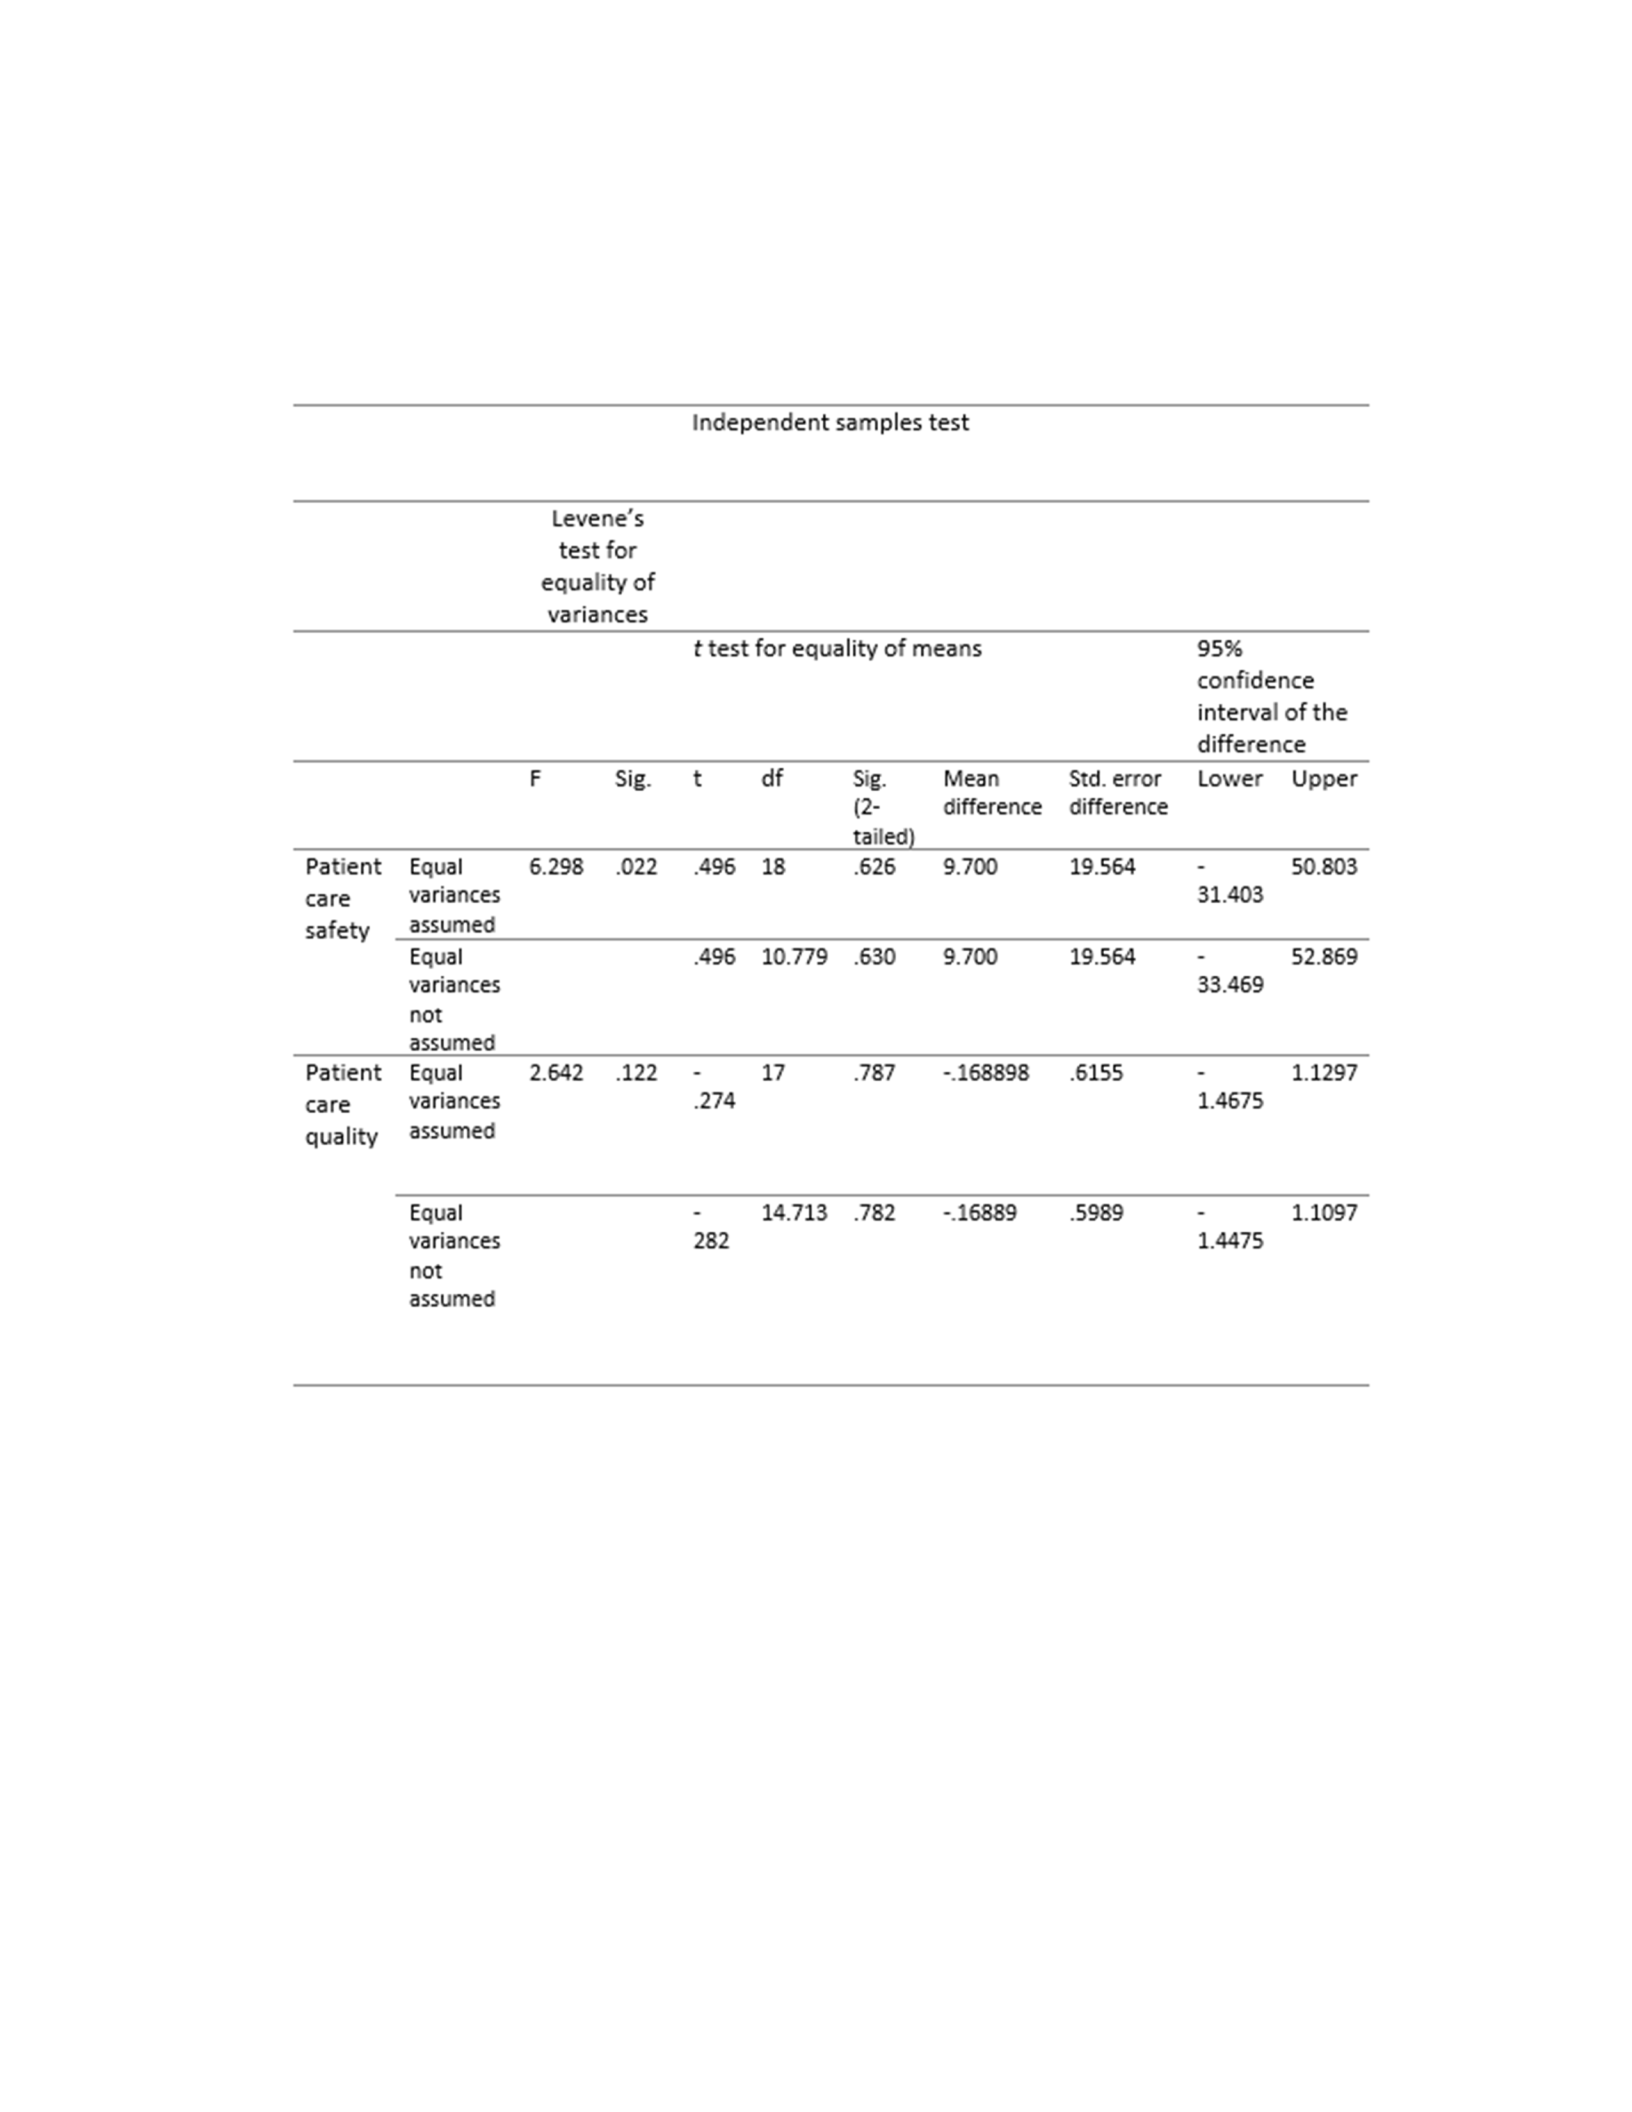
55
Table 3
Independent Sample Test
Logistic Regression
I used binary logistic regression analysis to assess the associations between SES
and patient care quality and safety. The importance of binary logistic regression is to
determine the extent to which independent variables predict the dependent variables and
affirm the “goodness-of-fit” test of the model. Table 4 outlines the observed versus
predicted outcome for hospital SES. The results suggest that six hospitals fell under the
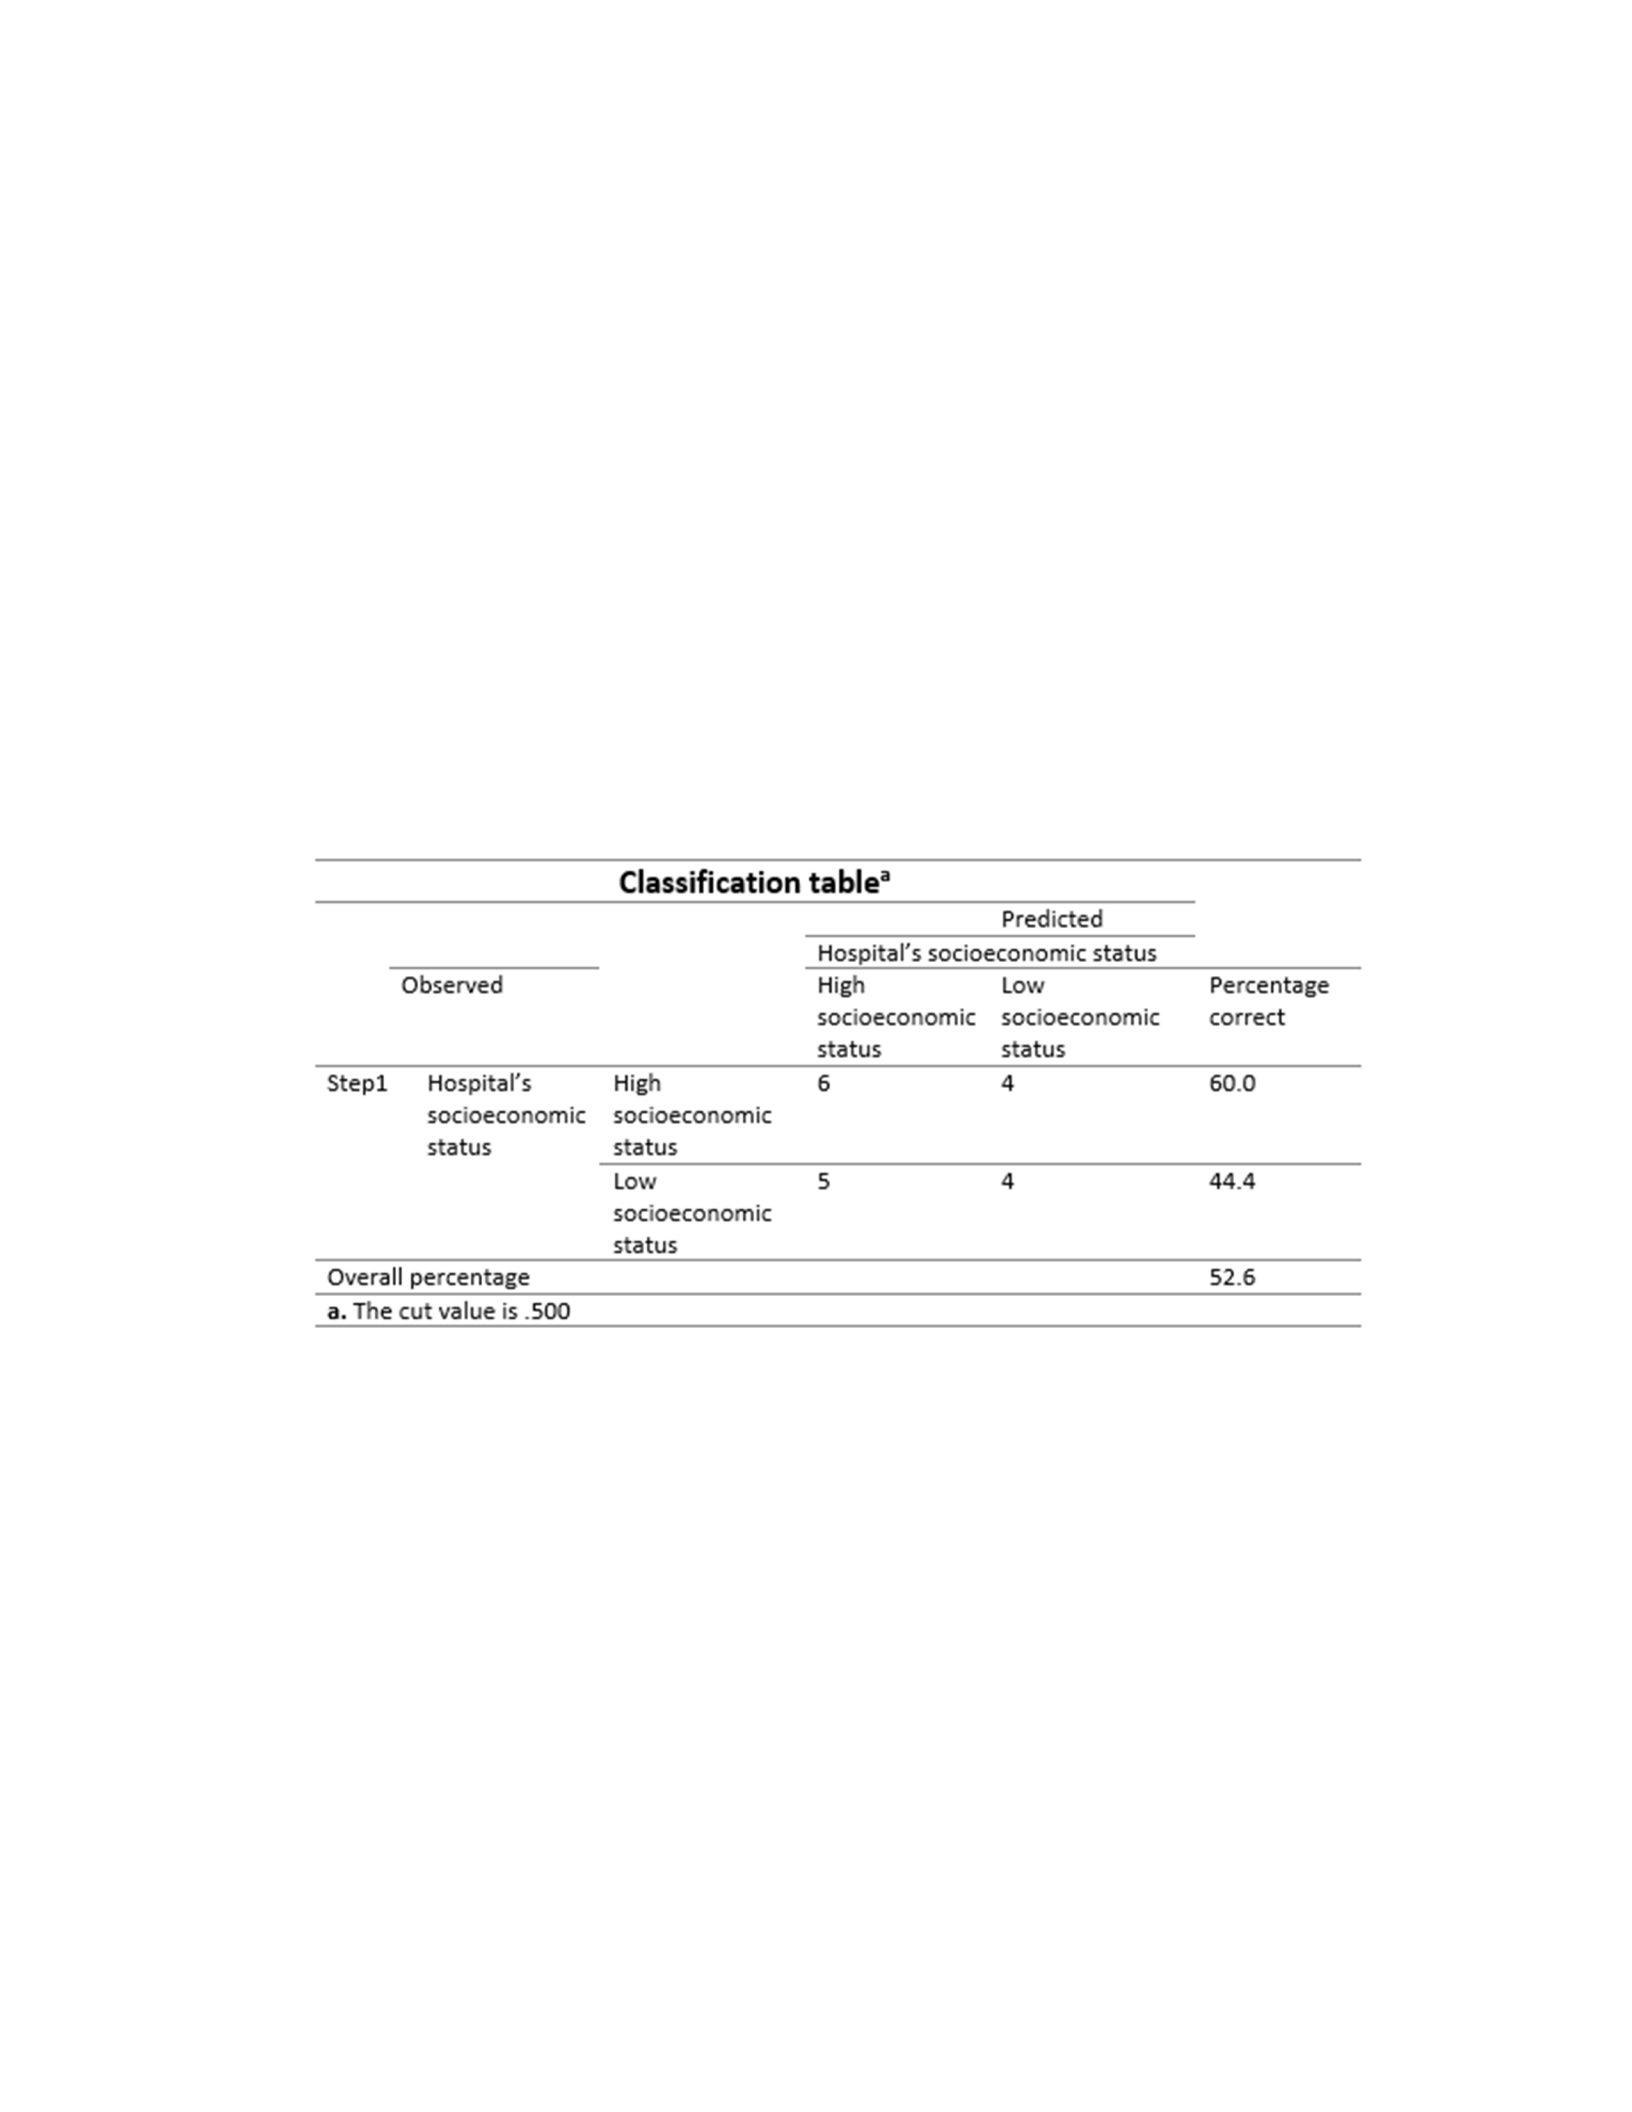
56
high-SES category while four fell in the low-SES category. The logistic regression model
indicated that out of 10 hospitals with a high SES, the prediction was correct six out of 10
times with a correct percentage of 60%. Additionally, the prediction had five acute care
hospitals in high-SES category and four in low-SES category, implying that the
prediction was correct five times out of nine with a correct percentage of 44.4%. The
overall correct percentage was 52.6%, suggesting that the model is of good fit.
Table 4
Classification Table
I used Table 5 to determine whether null hypotheses should be rejected and the
alternative hypotheses accepted or fail to reject both null hypotheses. The table displays a
comparative analysis of the independent variables against the dependent variables. The
outcome revealed that there was no significant association between patient care quality
and hospital’s SES p = .775 (p ≤ .05). The null hypothesis was not rejected as patient

57
care quality did not differ significantly between low-SES and high-SES acute care
hospitals.
Also, the outcome showed that there is no statistically significant association
between hospitals’ SES and patient care safety p = .536 (p ≤ .05). The null hypothesis
was, therefore, not rejected.
Table 5
Variables in the Equation
B S.E. Wald
df
Sig.
Exp(B)
95% C.I. for
EXP(B)
Lower
Upper
Step
1
a
Patient care safety -.007
.012 .384 1
.536
.993 .970 1.016
Patient care quality .105 .366 .082 1
.775
1.111 .542 2.277
Constant -
1.792
6.770
.070 1
.791
.167
a.
Variable(s) entered on step 1: Hospital-Acquired Infection, Average Hospital
Readmission Rate.
Summary
In this section, I presented the data collection outcomes, results from descriptive
statistics, independent samples test, and logistic regression analysis. In the study, I
examined whether patient care quality and patient care safety were related to hospitals’
SES in Chicago’s acute care hospitals. The results of the logistic regression model
showed the analysis was a correct fit and displayed the linkage between the dependent
variables and the independent variables. From the statistics, patient care quality did not
have any significant association with hospitals’ SES; hence, there was no difference in
patient care quality between hospitals of low SES and hospitals of high SES in Chicago’s
acute care hospitals. Also, the analysis of the independent variable of hospitals’ SES did

58
not exhibit any significant relationship with patient care safety. Thus, there was no
difference in patient care safety between hospitals of low SES and hospitals of high SES
in Chicago’s acute care hospitals. Further details of the outcomes of data analysis are
provided in Section 4.

59
Section 4: Applications to Professional Practice & Implications for Social Change
Introduction
The purpose of this quantitative study was to examine if patient care quality and
safety are related to hospitals’ SES among Chicago’s acute care hospitals. Two research
questions guided this study. Based on the results, both null hypotheses failed to be
rejected because there was no statistically significant association between hospitals’ SES
and patient care safety as well as no statistically significant association between
hospitals’ SES and patient care quality.
Interpretation of the Findings
The findings suggested that neither patient care quality nor patient care safety was
associated with hospitals’ SES. Studies that have investigated the impact of SES on
health care access found significant differences between health care access and quality of
care between individuals of low SES and those of high SES (McMaughan et al., 2020).
Zhang et al. (2021) found that patients from socially disadvantaged neighborhoods have a
higher likelihood of being hospitalized. In this study, however, I explored how hospitals’
SES impacted their provision of health care. The reference category for the SES of a
hospital in the current study was its eligibility status for Medicaid’s DSH payment
adjustments, whereby low-SES hospitals were assumed to qualify for DSH payments due
to their tendencies to serve patients from disproportionately disadvantaged backgrounds.
Nonetheless, it is worth mentioning that there were inconsistencies in data reporting for
most conditions used as proxies by several hospitals, which could have skewed the data.

60
Patient Care Quality and SES
The outcome of the study’s group statistics did not show difference between
patient care quality in low-SES acute care hospitals (M = 18.49, SD = .9400) and high-
SES acute care hospitals (M = 18.32, SD = 1.6138). The results of the independent
samples t test showed that there was no statistical significance between the differences in
hospitals’ SES and patient care quality p = .787 (p ≤ 0.05). As a result, the null
hypothesis failed to be rejected. For this study, I used the average rate of hospital
readmissions for select conditions to gauge patient care quality. This reiterates the
findings of Dharmarajan et al. (2013) who reported that the distribution of readmissions
for heart failure, acute myocardial infarction, and pneumonia was similar across high-
performing and low-performing hospitals. Similarly, Bernheim et al. (2016) compared
the risk-standardized readmission rates for hospitals caring for high- and low-categories
of patients in accordance with their Medicaid SES and did not find significant association
between SES and readmission rates. According to Silvestri et al. (2022), community level
factors, which include the SES of a hospital, did not have meaningful effect on the
number of hospital readmissions and did not affect hospital rankings.
Nonetheless, there are studies that have suggested SES has a direct influence on
the rate of hospital readmissions and affects the quality of health care (Gershon et al.,
2019). There are, however, measures that can be adopted by hospitals to reduce
readmission rates, which can explain the lack of association between hospitals’ SES and
patient care quality. Considering that majority of the hospital participants in the current
study could have adhered to quality measures of health care as envisaged by CMS, the

61
variations in quality measures did not have to be profound between the high-SES and
low-SES acute care hospitals. As per the CMS’s (2022) Hospital Readmissions
Reduction Program, all hospitals were encouraged to enhance communication and
improve coordination of care so as to avert preventable readmissions. With the small
sample size that was investigated in this study, it could be possible that all hospitals in the
study had strictly adhered to the norms required of them to engender high quality, safe
patient care. Moreover, the role of moderating factors, such as the number of registered
nurses at a hospital and the age of the hospital, could have influenced the strength of
association between hospitals’ SES and the dependent variables. For instance, a 10%
increase in the proportion of nurses at a hospital was found to reduce preventable deaths
and incidence of myocardial infarction, pneumonia, and surgical patients’ readmissions at
a hospital (McHugh & Ma, 2013). In that regard, this could be a possible limitation that
could have explained the association as expected if included as a variable.
Patient Care Safety and SES
Patient care safety is considered to vary between hospitals of low-SES and high-
SES. Hospitals of high SES are expected to have better strategies to enhance delivery of
safe health care than low SES hospitals (Arpey et al., 2017). Mo et al. (2019) found that
patients who acquired multidrug resistant nosocomial infections at different times in a
low-SES medical facility cited inadequate care as the main cause of HAIs. Low-SES
hospitals experience high incidences of HAIs due to financial challenges that may impede
access to high-quality medication and employment of adequate staff to provide safe and
timely care for patients.

62
In the current study, I did not find an association between patient care safety and
hospitals’ SES. The group statistics analysis between high-SES acute care hospitals (M =
39.70, SD = 58.994) and low-SES hospitals (M = 30.0, SD = 18.637) indicated that
patient care safety had low association with hospitals’ SES. This was consistent with the
results of the hypothesis test conducted using an independent samples t test. The null
hypothesis failed to be rejected because there was no statistically significant association
between hospitals’ SES and patient care safety p = .626 (p ≤ 0.05). The implication is
that the rates of HAIs did not statistically differ between low-SES and high-SES acute
care hospitals. Although Mo et al. (2019) utilized semi structured interviews to obtain the
perspectives of patients regarding their trauma regarding HAIs; I only used secondary
data of the selected HAIs at each facility. Furthermore, the sample considered in the
current study may not have been substantial enough to determine the strength and
direction of association between the variables.
Limitations of the Study
This study had some limitations based on its nature and design. First, the study
used secondary data, which may be a potential source of errors. Thompson (2017) stated
that reliance on secondary data as a source of records for research can plague a study with
human error because the data are researched and entered by another individual unknown
to the researcher. Second, the “pay for performance” model is designed in such a way
that it rewards health care providers and professionals for meeting specific set targets of
patient care quality and safety (Mathes et al., 2019). However, the urge to make a

63
positive impression on the public may tempt health care providers to be biased in their
data reporting, which can mask underlying cases of readmissions or HAIs.
Third, missing data in some of the study site hospitals could have limited the
outcomes of this study. For instance, some hospitals lacked data for readmission rates on
heart failure, heart attacks, and pneumonia, which possibly affected the true
representation of the variables’ outcomes.
The choice of the proxy factors used to measure hospitals’ SES for Chicago’s
acute care hospitals, patient care quality, and patient care safety was another possible
limitation of this study. There are other elements that can influence a hospital’s SES,
including hospital’s alignment of goals to engender a culture of excellence that results in
the realization of high-quality and safe patient care. Therefore, using hospitals’ eligibility
status for Medicaid DSH payment reduced the validity of the study and could have
affected the outcomes as well. Similarly, the readmission rates were reported in
percentages while the HAIs were given as a count of the cases observed, which may have
reduced internal validity of the study. Finally, the small sample size used in this study
posed a threat to the external validity of the study. The sample was also subjectively
chosen through convenience sampling, which may have failed to capture the true picture
of the scenario under investigation.
Recommendations
I outlined recommendations for further study on the topic with reference to the
outcomes of this study. The findings established that there was no association between
hospitals’ SES and patient care quality and safety. Future researchers should conduct

64
further exploration of this topic to establish if positive social change can result in
improved health care practices for acute care hospitals.
Confounding variables could have also influenced the outcomes of the findings of
this study. The methodology employed in the study could have overlooked the
complexity of the relationship between hospital’s SES and health care outcomes. For
instance, the number of registered nurses, which is a mediating variable of hospitals’
SES, could influence patient care outcomes, which determine the extent and severity of
readmissions for common comorbidities, such as pneumonia, heart attack, and heart
failure. I considered the number of registered nurses available for recruitment and
retaining at a health care facility to be a mediator of a hospital’s SES because low-SES
acute care hospitals may be limited in funding and have challenges in recruiting and
retaining professional nurses, which impacts health care administration (see Nayfeh &
Fowler, 2020). In addition, moderating variables, such as funding models, could have
influenced the strength of the relationship between low-SES and high-SES acute care
hospitals. Hospitals that have additional funding apart from Medicare or that provide
private insurance to patients could have better patient outcomes relative to the under-
resourced hospitals. Therefore, future research on this topic could include mediators and
moderators to explore the relationship beyond the simple association between SES as
independent variable and patient care quality and safety as dependent variables.
The other key limitation that could have impacted the outcomes of this study was
the use of proxy factors as the dependent variables. Patient care quality is a health care
outcome that is measured using different metrics, which can infer confusion and

65
complexity among different consumers of health care information (CMS, 2022). It is
likely that different hospitals report different measures, which was evident by the missing
data on readmission rates from some hospitals. Hospitals in low-socioeconomic
neighborhoods may not report certain measures, which will impact the comparison
between hospitals. This issue was also compounded by the small sample size used in the
current study. Future studies should employ diverse and large samples to cater for
hospital-wide differences in data reporting and moderate the effect of missing data in
some hospitals.
Implications for Professional Practice and Social Change
In this section, I provide the implications concerning professional practices and
social change with regard to the association of hospitals’ SES with patient care quality
and safety. Two proxy indicators were used in this study to measure the outcomes of
patient care quality and safety in the acute care hospitals: hospital readmission rates and
HAIs. The quality and safety of health care are essential measures in the assessment of
health care outcomes and patient experiences. Acute care hospitals should adopt effective
communication and organized workflow to boost the effectiveness of physicians and
nurses in averting preventable HAIs and reduce readmissions for ailments, such as
pneumonia, heart failure, and heart attack. Although the findings did not show any
significant association between (a) hospitals’ SES and patient care quality, and (b)
hospitals’ SES and patient care safety, significant lessons for professional practice and
for social change can be adopted to ensure equity of access to high quality and safe
patient care across all acute care hospitals.

66
Professional Practice
Based on the findings of this study, several professional practices can be
considered to enhance health care equity in terms of patient care quality and safety
between low-SES and high-SES hospitals. The seriousness of using patient care quality
and safety as a metric of concern in health care is underscored by the IDPH (2022),
which argued that up to 98,000 Americans succumb each year to preventable illnesses
that result from medical errors. This costs the government over $17 billion dollars
annually in compensations for medical errors, contributing to an increase in costs to
health care consumers (Warchol et al., 2019). The findings in the current study indicated
that there is no significant association between hospitals’ SES and patient care safety, p =
.626 (p ≤ 0.05). Similarly, the analysis of group statistics in high-SES acute care hospitals
(M = 39.70, SD = 58.994) and low-SES hospitals (M = 30.0, SD = 18.637) suggested that
there was low association between patient care safety and hospitals’ SES.
In collaboration with the Centers for Disease Control and Prevention (CDC), the
IDPH has plans to reduce HAIs to improve safety of health care in acute care hospitals in
the state of Illinois (IDPH, 2016). In its action plan, the IDPH outlined fundamental
interventions that can be adapted by acute care hospitals to reduce HAIs, thereby
improving patient care safety. These strategies include following standard and
transmission-based measures, using personal protective equipment appropriately,
performing hand hygiene regularly and as expected, disinfecting medical appliances
while discarding used ones appropriately, maintaining a clean working environment, and
maintaining proper communication (IDPH, 2016). In reference to the findings of this

67
study, health care leaders, including the leadership of nurses, is required to carry out
training and education of health care professionals to equip them with knowledge and
competencies to detect, investigate, and respond to infectious outbreaks, such as
community HAIs and antimicrobial resistance.
Regarding patient care quality, the rate of hospital readmissions for patients
suffering from select conditions need to be further reduced. Some of the strategies are
those that focus on the socioeconomic factors that impede low-income patients from
accessing health care on time, which exacerbates conditions and result in increased
likelihood of readmissions. Warchol et al. (2019) recommended two strategies that can be
used by health care leaders in acute care hospitals to reduce hospital readmissions for
preventable conditions. First, the authors contended that data analytics can help acute
care hospitals to predict with accuracy the likelihood of readmissions and develop
discharge protocols that help in preventing avoidable cases of readmissions. Second,
acute care hospitals can use electronic health records to discover pertinent issues
regarding patients’ conditions. Acute care hospitals may then use information obtained
from electronic records to frame the structure of patients’ diagnoses and referrals, helping
to prevent avoidable readmissions. These strategies, if effectively reinforced by the IDPH
through its action plan on reducing HAIs and the number of 30-day readmissions, could
help acute care hospitals to improve patient care quality and safety across the continuum
of care.

68
Methodological
There are extant methodological opportunities that could be employed to improve
the internal and external validity of future studies on this topic. Future studies can use a
larger sample size while employing a principal component analysis of the hospital’s SES
to develop a composite hospital’s SES. Additionally, principal component analysis could
be used to measure patient care quality and safety by utilizing the core measures of
quality and safety of health care, including 30-day readmissions for the select conditions,
risk-adjusted inpatient mortality, 30-day mortality, indicators of patient safety from
inpatient admissions, inpatient days by category of service, process of care chart review,
patient characteristics, CMS pay for performance score of the hospital, and patient
experience surveys. I believe the inclusion of additional covariates would provide rigor to
the future study and help in pinpointing the strength and direction of association between
the independent variable and dependent variables of the current study.
Theoretical
This study was anchored on the DQF. The suitability of DQF to this study is
underpinned by its focus on the quality of interactions between the physician and his/her
patients (Allen-Duck et al., 2017). The DQF provides three elements of quality of health
care: structure, processes, and outcomes (Binder et al., 2021). Structures include the
portrait of the place where health care occurs, including the equipment, instruments,
standards, practices, and staffing; processes define the events such as counseling,
medication, therapy; while the outcome entail the impact of the provided healthcare to the
selected population. Understanding the synergy of relationship between these elements

69
and how they influence the quality of health care is significant in outlining strategies that
can be adopted to reduce discrepancies in the quality and safety of health care between
low-SES and high-SES acute care hospitals in Chicago, Illinois. Structures can include
the number of health care professionals, such as the number of registered nurses.
Therefore, future studies can enhance the rigor of the study through comprehensive
analysis of the relationship between hospitals’ SES and quality and safety of patient care
by integrating the role of mediators and moderators in the research. Lack of mediating
and moderating variables is one of the limitations that could have affected the validity of
this study. For a holistic analysis of how SES influences quality and safety of care, future
studies should explore the relationship between the variables examined in the current
study by considering their impact on the strength and direction of the relationship.
Empirical
While this study failed to reject the null hypotheses for both research questions,
the onus is upon future researchers to find out the effect of hospitals’ SES on quality and
safety of care through integration of other variables. Additionally, the sample size can be
increased to broaden external validity. Instead of focusing on few proxy indicators, future
studies can utilize principal component analysis to analyze how various indicators of
patient care quality and patient care safety are associated with the hospitals’ SES.
Positive Social Change
In tandem with the Walden University’s mission of tying the students’ research
with positive social change implications, the findings of this study may be used to
accomplish positive social change through proven strategies to enhance quality and safety

70
of patient care in acute care hospitals. Although I did not find significant association
between hospitals’ SES with patient care quality and safety, social support programs may
focus on all areas of hospitals’ SES with patient care quality and safety. All acute care
hospitals can use the findings of this study to dissociate hospital’s SES from the quality
and safety of patient care. The results suggest that individual hospital factors, excluding
SES, linked to the prevention of patients’ readmissions and HAIs may be attributed for
high or poor patient care quality and safety.
Hospital factors that affect the culture of patient safety are important in
understanding the role of individualized quality care in acute care hospitals. In Mihdawi
et al. (2020), staffing, adequate resources, nurses’ participation and advancement, and
effective workplace communication significantly affected the quality of care provided to
patients. Nurses form an important component of patients’ recovery process; thus an
inclusion of nurses in the making of decisions related to patient management is
fundamental to enhancing patient safety. Where acute care hospitals are understaffed,
quality of care could be compromised. In order to conduct investigations regarding HAI
outbreaks and to leverage surveillance data for effective public health response, acute
care hospitals require adequate and well-trained health professionals who can accelerate
provision of quality care across the spectrum of care in all HAI prevention units. The
current study could be used to create awareness on holistic approaches that may be
adopted by acute care hospitals to improve patient care quality and safety without
associating it with the SES of hospitals.

71
Additionally, acute care hospitals could adopt patient-centric models of care to
improve the quality of patient experience with health care. According to Bellio and
Buccoliero (2021), patients’ satisfaction is affected by the blending of positive patient
experiential factors. The perception of high quality of physical environment positively
impacts patients’ experiential satisfaction, with quality of patients’ empowerment through
dignified patient-doctor relationship mediating this relationship. This implies that acute
care hospitals should work on other factors that increase patients’ experiential satisfaction
in order to improve the quality and safety of patient care. This study is consistent with the
findings of Kuipers et al. (2019) where patient-centric care was found to increase health
care outcomes. These practices may enable acute care hospitals to reduce the number of
readmissions for select conditions and to prevent HAIs.
At the individual level, acute care hospitals in Chicago can adopt standard
transmission-based precautions, provide adequate protective personal equipment for
health professionals, create awareness on hygiene maintenance, and support organized
communication to encourage preventive measures against HAI outbreaks and avoidable
readmissions (IDPH, 2016). As a family of acute care hospitals, recent findings suggest
that HAIs pose significant threat to patient safety and threaten the fiscal viability of acute
care hospitals under pay-for-performance system (Vokes et al., 2018). As a result,
positive social change may be realized with the use of empirical practices aimed at
reducing hospital-acquired infections in acute care hospitals. The management of acute
care facilities should support frontline providers and infection control staff such as nurses
to enhance the adoption of practices that prevent and reduce HAIs from occurring.

72
Horizontal infection strategies such as hand hygiene, central line insertion bundles, and
provision of safety checklists to be followed by staff in acute care hospitals may result in
positive social impact across the spectrum of care in Chicago’s acute care hospitals.
At the organizational level, improving communication has been found to enhance
the transfer and adoption of best practices in hospitals. IDPH (2016) argues that effective
communication across the spectrum of care is crucial in expediting the implementation of
interventions to reduce hospital readmissions and to prevent HAIs. The employment of
communication interventions at discharge were found to result in significantly reduced
rates of hospital readmissions and increased adherence to treatment, which improved
patients’ experiential satisfaction with care (Becker et al., 2021). Therefore, acute care
hospitals should strive to establish communication with clients before and after discharge
to achieve improved health care outcomes.
At the society level, the adoption of best practices to prevent HAIs and
antimicrobial resistance as advocated by the IDPH should be prioritized by all acute care
hospitals, regardless of their SES, to improve the quality and safety of patient care.
Education for policy makers, hospital administrators, as well as community members
may achieve significant results in reducing the number of cases of readmission for the
select conditions. Improvement of patient care quality and safety across all acute care
hospitals may also lead to reduced cases of HAIs.
Conclusion
Several studies have focused on the relationship between SES of patients and their
health; however, there is paucity of quantitative research regarding the relationship

73
between the SES of acute care hospitals with patient care quality and safety. This study is
unique for examining whether patient care quality and patient care safety are related to
hospitals’ SES in Chicago’s acute care hospitals. Although the findings did not support
any statistical association between hospitals’ SES with patient care quality and safety,
this study has provided the impetus for a more rigorous research that considers the
moderators and mediators of hospitals’ SES in influencing quality and safety of patient
care in acute care hospitals. Future studies can build on the findings of this study to
explore the relationship between patient care quality and safety with hospitals’ SES.

74
References
Abubakar, M. I., & Kathuria, K. (2020). Performance of public healthcare services
organizations in Nigeria: A literature review. EC Nursing and Healthcare, 2, 176-
183.
Adams, D. (2017). Rural and urban healthcare issues. Issues and Trends in Nursing, 425.
Ahmed, S., Shommu, N. S., Rumana, Barron, G. R., Wicklum, S., & Turin, T. C. (2016).
Barriers to access of primary healthcare by immigrant populations in Canada: A
literature review. Journal of Immigrant and Minority Health, 18(6), 1522-1540.
https://doi.org/10.1007/s10903-015-0276-z
Alhassan, R. K., Duku, S. O., Janssens, W., Nketiah-Amponsah, E, Spieker, N., van
Ostenberg, P., & de Wit, T. F. R. (2015). Comparison of perceived and technical
healthcare quality in primary health facilities: Implications for sustainable
National Health Insurance Scheme in Ghana. Plos One, 10(10),
https://doi.org/10.1371/joarnal.pone.0140109
Allen-Duck, A., Robinson, J. C., & Stewart, M. W. (2017). Healthcare quality: A concept
analysis. Nursing Forum, 52(4), 377-386.
Allen, H., Gordon, S. H., Lee, D., Bhanja, A., & Sommers, B. D. (2021). Comparison of
utilization, costs, and quality of Medicaid vs subsidized private health insurance
for low-income adults. JAMA Network Open, 4(1), e2032669-e2032669
American College of Healthcare Executives. (2022). Top issues confronting hospitals in
2021. https://www.ache.org/learning-center/research/about-the-field/top-issues-
confronting-hospitals/top-issues-confronting-hospitals-in-2021.

75
Amoah, P. A., Edusei, J., & Amuzu, D. (2018). Social networks and health:
Understanding the nuances of healthcare access between urban and rural
populations. International Journal of Environmental Research and Public
Health, 15(5), 973. https://doi.org/10.3390/ijerph15050973
Andersen, R. M., & Davidson, P. L. (2007). Improving access to care in America:
Individual and contextual Indicators. In R. M. Andersen, T. H. Rice, & G. F.
Kominski (Eds.), Changing the U.S. health care system: Key issues in health
services policy and management (pp. 3–31). Jossey-Bass.
Arpey, N., Gaglioti, A., & Rosenbaum, M. (2017). How socioeconomic status affects
patient perceptions of health care: A qualitative study. Journal of Primary Care &
Community Health, 8(3), 169-175. https://doi.org/10.1177/2150131917697439
Babitsch, B., Gohl, D., & von Lengerke, T. (2012). Re-revisiting Andersen’s behavioral
model of health services use: A systematic review of studies from 1998–
2011. GMS Psycho-Social-Medicine, 9(Special issue), 1-15.
https://doi.org/10.3205/psm000089
Becker, C., Zumbrunn, S., Beck, K., Vincent, A., Loretz, N., Müller, J., Amacher, S. A.,
Schaefert, R., & Hunzikier, S. (2021). Interventions to improve communication at
hospital discharge and rates of readmission. JAMA Network Open, 4(8),
e2119346. https://doi.org/10.1001/jamanetworkopen.2021.19346
Bellio, E., & Buccoliero, L. (2021). Main factors affecting perceived quality in
healthcare: A patient perspective approach. The TQM Journal, 33(7), 176-192.
https://doi.org/10.1108/tqm-11-2020-0274

76
Bernheim, S. M., Parzynski, C. S., Horwitz, L., Lin, Z., Araas, M. J., Ross, J. S., Drye, E.
E., Suter, L. G., Normand, S. T., & Krumholz, H. M. (2016). Accounting for
patients’ socioeconomic status does not change hospital readmission rates. Health
Affairs, 35(8), 1461-1470. https://doi.org/10.1377/hlthaff.2015.0394
Berwick, D, & Fox, D. M. (2016). Evaluating the quality of medical care: Donabedian’s
classic article 50 years later. The Milbank Quarterly, 94(2), 237-241.
https://doi.org/10.1111/1468-0009.12189
Bhatt, J. & Bathija, P. (2018). Ensuring access to quality health care in vulnerable
communities. Academic Medicine, 93(9), 1271.
Binder, C., Torres, R.E., & Elwell, D. (2021). Use of the Donabedian model as a
framework for COVID-19 response at a hospital in suburban Westchester County,
New York: A facility-level case report. Journal of Emergency Nursing, 47(2),
239-255. https://doi.org/10.1016/j.jen.2020.10.008
Boersma, P., Black, L. I., & Ward, B. W. (2020). Prevalence of multiple chronic
conditions among US adults, 2018. Preventing Chronic Disease, 17.
https://doi.org/10.5888/pcd17.200130
Boland, A., Cherry. G., & Dickson, R. (Eds.). (2017). Doing a review. A student's guide.
Sage Press.
Burns, L. R., & Pauly, M. V. (2018). Transformation of the health care industry: Curb
your enthusiasm? The Milbank Quarterly, 96(1), 57–109.
https://doi.org/10.1111/1468-0009.12312

77
Carlson, K. A., & Winquist, J. R. (2017). Independent samples t. In K. Carlson & J.
Winquist (Eds.), An introduction to statistics: An active learning approach (2nd
ed., pp. 315-330). Sage Publications.
https://us.sagepub.com/sites/default/files/upm-
assets/79653_book_item_79653.pdf
Casanave, C. P., & Li, Y. (2015). Novices’ struggles with conceptual and theoretical
framing in writing dissertations and papers for publication dagger. Publications,
3(2), 104-119.
Centers for Disease Control and Prevention. (2021). Healthcare associated infections
(HAIs). https://www.cdc.gov/hai/index.html.
Centers for Medicare & Medicaid Services. (n.d.). CMS data navigator glossary of terms.
https://www.cms.gov/Research-Statistics-Data-and-
Systems/Research/ResearchGenInfo/Downloads/DataNav_Glossary_Alpha.pdf
Centers for Medicare & Medicaid Services. (2022). Core measures.
https://www.cms.gov/Medicare/Quality-Initiatives-Patient-Assessment-
Instruments/QualityMeasures/Core-Measures.
Centers for Medicare & Medicaid Services. (2022). Disproportionate share hospital
(DSH). https://www.cms.gov/Medicare/Medicare-Fee-for-Service-
Payment/AcuteInpatientPPS/dsh
Centers for Medicare & Medicaid Services. (2022). Find & compare nursing homes,
hospitals & other providers near you. https://www.medicare.gov/care-
compare/?providerType=Hospital&redirect=true.

78
Centers for Medicare & Medicaid Services. (2022). Hospital Readmissions Reduction
Program (HRRP). https://www.cms.gov/Medicare/Medicare-Fee-for-Service-
Payment/AcuteInpatientPPS/Readmissions-Reduction-Program.
Centers for Medicare & Medicaid Services. (2021). Medicare disproportionate share
hospital. https://www.cms.gov/outreach-and-education/medicare-learning-
network-mln/mlnproducts/downloads/disproportionate_share_hospital.pdf.
Cheng, H. G., & Phillips, M. R. (2014). Secondary analysis of existing data:
Opportunities and implementation. Shanghai Archives of Psychiatry, 26(6), 371-
375. https://doi.org/10.11919/jissn.1002-0829.214171
Cohen, C. C, & Shang, J. (2015). Evaluation of conceptual frameworks applicable to the
study of isolation precautions effectiveness. Journal of Advanced Nursing, 71(10),
2279-2292. https://doi.org/10.1111/jan.12718
Collins, A. S. (2008). Preventing health care-associated infections. In R. Hughes
(Ed.), Patient safety and quality: An evidence-based handbook for nurses. Agency
for Healthcare Research and Quality.
https://www.ncbi.nlm.nih.gov/books/NBK2683/
Creswell, J. W., & Creswell. J. D. (2018). Research design: Qualitative, quantitative, and
mixed methods (5th ed.). Sage.
Cuomo, A., Koukouna, D., Macchiarini, L., & Fagiolini, A. (2021). Patient safety and
risk management in mental health. Textbook of Patient Safety and Clinical Risk
Management, 287-298.
79
Cyr, M. E., Etchin, A. G., Guthrie, B. J., & Benneyan, J. C. (2019). Access to specialty
healthcare in urban versus rural US populations: A systematic literature review.
BMC Research, 19(1), 1-17. https://doi.org/10.1186/02913-0194815-5
Das, L. (2017). Role of data in improving care within a health system. RAND
Corporation. https://doi.org/10.7249/RGSD39
Dharmarajan, K., Hsieh, A., Lin, Z., Bueno, H., Ross, J. S., Horwitz, L. I., Barreto-Filho,
J. A., Kim, N., Suter, L. G., Bernheim, S. M., Drye, E. E., & Krumholz, H. M.
(2013). Hospital readmission performance and patterns of readmission:
retrospective cohort study of Medicare admissions. BMJ, 347(nov19 23), f6571-
f6571. https://doi.org/10.1136/bmj.f6571
Donahoe, J. T., & McGuire, T. G. (2020). The vexing relationship between
socioeconomic status and health. Israel Journal of Health Policy Research, 9(1).
https://doi.org/10.1186/s13584-020-00430-0
Du, M., Cheng, L., Li, X., & Yang, J. (2020). Factors affecting the travel mode choice of
the urban elderly in healthcare activity: Comparison between core area and
suburban area. Sustainable Cities and Society, 52, 101868.
Eathington, L. 2000-2009 Population growth in the Midwest: Urban and rural dimensions
(2010). Publications from USDA-ARS / UNL Faculty. 811.
https://digitalcommons.unl.edu/usdaarsfacpub/811
Eyisi, D. (2016). The Usefulness of qualitative and quantitative approaches and methods
in researching problem-solving ability in science education curriculum. Journal of

80
Education and Practice, 7(15), 91–100.
https://files.eric.ed.gov/fulltext/EJ1103224.pdf.
Fausto, M., Bousquat, A, Lima, J., Giovanella, L, Almeida, P., Mendonça, M., (2017).
Evaluation of Brazilian primary healthcare from the perspective of the users:
Accessible, continuous, and acceptable? The Journal of Ambulatory Care
Management, 560-570. https://doi.org/10.1097/JAC.0000000000000183
Ferro, E.G., Secemsky, E.A., Wadhera, R.K., Choi, E., Strom, J.B., Wasfy, J.H., Wang,
Y., Shen, C. & Yen, R.W. (2019). Patient readmission rates for all insurance types
after implementation of the Hospital Readmissions Reduction Program. Health
Affairs, 38(4), 585-593. https://doi.org/10.1377/hlthaff.2018.05412
Freeman, V. L, Naylor, K. B., Boylan, E. E., Booth, B. J., Pugach, O., Barrett. R. E., &
McLafferty, S. L. (2020). Spatial access to primary care providers and colorectal
cancer-specific survival in Cook County, Illinois. Cancer Medicine 12(3), 12-18.
Galama, T. J., & Van Kippersluis, H. (2019). A theory of socio-economic disparities in
health over the life cycle. The Economic Journal, 129(617), 338-374.
Garchitorena, A., Sokolow, S. H., Roche, B., Ngonghala, C. N., Jocque, M., Lund, A.,
Barry, M., Mordecai, E. A., Daily, G. C., Jones, J. H., Andrews, J. R., Bendavid,
E., Luby, S. P., LaBeaud, A. D., Seetah, K., Guégan, J. F., Bonds, M. H., & De
Leo, G. A. (2017). Disease ecology, health and the environment: A framework to
account for ecological and socio-economic drivers in the control of neglected
tropical diseases. Philosophical transactions of the Royal Society of London.

81
Series B, Biological sciences, 372(1722), 20160128.
https://doi.org/10.1098/rstb.2016.0128
Garcia, C. D. L., Abreu, L. C. D., Ramos, J. L. S., Castro, C. F. D. D., Smiderle, F. R. N.,
Santos, J. A. D., & Bezerra, I. M. P. (2019). Influence of burnout on patient
safety: Systematic review and meta-analysis. Medicina, 55(9), 553.
https://doi.org/10.3390%2Fmedicina55090553
Gershon, A. S., Thiruchelvam, D., Aaron, S., Stanbrook, M., Vozoris, N., Tan, W. C.,
Cho, E., & To, T. (2019). Socioeconomic status (SES) and 30-Day hospital
readmissions for chronic obstructive pulmonary (COPD) disease: A population-
based cohort study. PLOS ONE, 14(5).
https://doi.org/10.1371/journal.pone.0216741
Gilchrist, M., & Samuels, P. (2014). Independent Samples t-test.
https://www.researchgate.net/publication/274635481_Independent_Samples_t-
test
Gonzalo, J. D., Dekhtyar, M., Starr, S. R., Borkan, J., Brunett, P., Fancher, T., & Monrad,
S. (2017). Health systems science curricula in undergraduate medical education:
identifying and defining a potential curricular framework. Academic Medicine,
92(1), 123-131. https://doi.org/10.1097/ACM.0000000000001177
Gornick, M. E. (2002). Measuring the effects of socioeconomic status on health care. In
Guidance for the National Healthcare Disparities Report (pp. 45–73). National
Academies Press.

82
Gqaleni, T. M., & Bhengu, B. R. (2020). Analysis of patient safety incident reporting
system as an indicator of quality nursing in critical care units in KwaZulu-Natal,
South Africa. Health SA Gesondheid (Online), 25, 1-8.
Han, K. T., Park, E. C., & Kim, S. J. (2016). Unmet healthcare needs and community
health center utilization among the low-income population based on a nationwide
community health survey. Health Policy (Amsterdam, Netherlands), 120(6), 630–
637. https://doi.org/10.1016/j.healthpol.2016.04.004
Heider, D., Matschinger, H., Müller, H., Saum, K., Quinzler, R., Haefeli, W.E., Wild, B.,
Lenhert, T., Brenner, H., & König, H. (2014). Health care costs in the elderly in
Germany: An analysis applying Andersen’s behavioral model of health care
utilization. BMC Health Services Research, 14(71). https://doi.org/10.1186/1472-
6963-14-71
Hewner, S., Casucci, S., & Castner, J. (2016). The roles of chronic disease complexity,
health system integration, and care management in post-discharge healthcare
utilization in a low-income population. Research in Nursing & Health, 39(4),
215–228. https://doi.org/10.1002/nur.21731
Hong, Y., Samuels, S.K., Huo, J., Lee, N., Mansoor, H., & Duncan, R. (2019). Patient-
centered care factors and access to care: A path analysis using the Andersen
behavior model. Public Health, 171, 41-49.
https://doi.org/10.1016/j.puhe.2019.03.020
Howard-Anderson, J., Busuttil, A., Lonowski, S., Vangala, S., & Afsar-Manesh, N.
(2016). From discharge to readmission: Understanding the process from the

83
patient perspective. Journal of Hospital Medicine, 11(6), 407–412.
https://doi.org/10.1002/jhm.2560
Huber, E., Kleinknecht‐Dolf, M., Kugler, C., & Spirig, R. (2021). Patient‐related
complexity of nursing care in acute care hospitals–an updated
concept. Scandinavian Journal of Caring Sciences, 35(1), 178-195.
Ilinca, S., Di Giorgio, L, Salari, P., & Chuma, J. (2019). Socio-economic inequality and
inequity in use of health care services in Kenya: evidence from the fourth Kenya
household health expenditure and utilization survey. International Journal for
Equity in Health, 18(1), 196-199.
Illinois Department of Healthcare and Family Services (HFS). (2022). Hospital
Reimbursement Notifications.
https://www2.illinois.gov/hfs/MedicalProviders/MedicaidReimbursement/Pages/d
sh.aspx.
Illinois Department of Public Health. (2016). Illinois action plan to prevent health care
associated infections and antimicrobial resistance.
https://dph.illinois.gov/content/dam/soi/en/web/idph/files/publications/publication
soppsil-action-plan-prevent-haier.pdf
Illinois Department of Public Health. (2022). Illinois Center for Health Statistics
Database and Datafile Resource Guide.
https://idph.illinois.gov/oehsd/ddrg/public/genericdb/code/GenericList.asp.

84
Illinois Department of Public Health. (2021). IL Hospital Report Card & Consumer
Guide to Health Care. https://dph.illinois.gov/topics-services/prevention-
wellness/patient-safety-quality/il-hospital-report-card.html.
Illinois Department of Public Health. (2022). Patient safety & quality.
https://dph.illinois.gov/topics-services/prevention-wellness/patient-safety-
quality.html.
J. Wickham, R. (2019). Secondary analysis research. Journal of the Advanced
Practitioner in Oncology, 10(4), 395-400.
https://doi.org/10.6004/jadpro.2019.10.4.7
Kabir, M.R. (2021). Adopting Andersen’s behavior model to identify factors influencing
maternal healthcare service utilization in Bangladesh. PLOS ONE, 16(11),
e0260502. https://doi.org/10.1371/journal.pone.0260502
Kabisch, N. (2019). The influence of socio-economic and socio-demographic factors in
the association between urban green space and health. In Biodiversity and Health
in the Face of Climate Change (pp. 91-119). Springer Press.
Kang, H. (2021). Sample size determination and power analysis using the G*Power
software. Journal of Educational Evaluation for Health Professions, 18(17).
https://doi.org/10.3352/jeehp.2021.18.17
Kim, H., & Lee, M. (2016). Factors associated with health services utilization between
the years 2010 and 2012 in Korea: Using Andersen's behavioral model. Osong
Public Health and Research Perspectives, 7(1), 18-25.
https://doi.org/10.1016/j.phrp.2015.11.007
85
Koch, A. R., & Geller, S. E. (2019). Racial and ethnic disparities in pregnancy-related
mortality in Illinois, 2002-2015. Journal of Women's Health, 28(8), 1153-1160.
Koesters, M., Barbui, C., & Purgato, M. (2018). Recent approaches to provision of
mental healthcare in refugee populations. Current Opinion in Psychiatry, 31(4),
368-372.
Kuipers, S.J., Cramm, J.M., & Nieboer, A.P. (2019). The importance of patient-centered
care and co-creation of care for satisfaction with care and physical and social
well-being of patients with multi-morbidity in the primary care setting. BMC
Health Services Research, 19(1). https://doi.org/10.1186/s12913-018-3818-y
Kuriyan, A., Kinkler, G., Cidav, Z., Kang-Yi, C., Eiraldi, R., Salas, E., & Wolk, C. B.
(2021). Team strategies and tools to enhance performance and patient safety
(TeamSTEPPS) to improve collaboration in school mental health: Protocol for a
mixed methods hybrid effectiveness-implementation study. JMIR Research
Protocols, 10(2), e26567. https://doi.org/10.2196/26567
Jin, Y., Zhu, W., Zhang, Y., Ling, X. U., & Meng, Q. (2017). Impact of health resources
allocation on healthcare seeking behavior among inpatients in China. Chinese
Journal of Health Policy, 10(9), 51-56. https://doi.org/10.1186/s12939-017-0576-
0
Jordans, M. J. D., Luitel, N. P., Kohrt, B. A., Rathod, S. D., Garman, E. C., De Silva, M.,
Komproe, I. H., Patel, V., & Lund, C. (2019). Community-, facility-, and
individual-level outcomes of a district mental healthcare plan in a low-resource

86
setting in Nepal: A population-based evaluation. PLoS Medicine, 16(2),
e1002748. https://doi.org/10.1371/journal.pmed.1002748
Lawati, M. H. A., Dennis, S., Short, S. D., & Abdulhadi, N. N. (2018). Patient safety and
safety culture in primary health care: A systematic review. BMC Family
Practice, 19(1), 1-12.
Liu, X. S., Carlson, R., & Kelley, K. (2019). Common language effect size for
correlations. The Journal of General Psychology, 146(3), 325–338.
https://doi.org/10.1080/00221309.2019.1585321
Liu, Y., Zhong, L., Yuan, S., & van de Klundert, J. (2018). Why patients prefer high-
level healthcare facilities: A qualitative study using focus groups in rural and
urban China. BMJ Global Health, 3(5). http://orcid.org/0000-0001-7384-1351
Lopez, E., Neuman, T., Jacobson, G., & Levitt, L. (2020). How much more than
Medicare do private insurers pay? A review of the literature. San Francisco:
Kaiser Family Foundation. https://www.elmcgroup.com/sequoia/wp-
content/uploads/2020/05/How-Much-More-Than-Medicare-Do-Private-Insurers-
Pay_-A-Review-of-the-Literature-_-KFF.pdf
LoPorto, J. (2020). Application of the Donabedian quality-of-care model to New York
State direct support professional core competencies: How structure, process, and
outcomes impacts disability services. Journal of Social Change, 12(1), 40-70.
https://doi.org/10.5590/josc.2020.12.1.05
Lund, A. (2021). The ultimate IBM SPSS statistics guide.
https://statistics.laerd.com/features-overview.php
87
Manzanera, R., Moya, D., Guilabert, M., Plana, M., Gálvez, G., Ortner, J., & Mira, J. J.
(2018). Quality assurance and patient safety measures: A comparative
longitudinal analysis. International Journal of Environmental Research and
Public Health, 15(8), 1568. https://doi.org/10.3390/ijerph15081568
Mathes, T., Pieper, D., Morche, J., Polus, S., Jaschinski, T., & Eikermann, M. (2019).
Pay for performance for hospitals. The Cochrane Database of Systematic
Reviews, 7(7), CD011156. https://doi.org/10.1002/14651858.CD011156.pub2
McHugh, M., & Ma, C. (2013). Hospital nursing and 30-day readmissions among
Medicare patients with heart failure, acute myocardial infarction, and
pneumonia. Medical Care, 51(1), 52-59.
https://doi.org/10.1097/mlr.0b013e3182763284
McMaughan, D. J., Oloruntoba, O., & Smith, M. L. (2020). Socioeconomic status and
access to health care: Interrelated drivers for healthy aging. Frontiers in Public
Health, 8, 231. https://doi.org/10.3389/fpubh.2020.00231
Mihdawi, M., Al-Amer, R., Darwish, R., Randall, S., & Afaneh, T. (2020). The influence
of nursing work environment on patient safety. Workplace Health &Amp;
Safety, 68(8), 384-390. https://doi.org/10.1177/2165079920901533
Mitchell, P.H. (2008). Defining patient safety and quality care. In R. Hughes, Patient
safety and quality: An evidence-based handbook for nurses. Agency for
Healthcare Research and Quality.
https://www.ncbi.nlm.nih.gov/books/NBK2681/.

88
Mo, Y., Low, I., Tambyah, S., & Tambyah, P. (2019). The socio-economic impact of
multidrug-resistant nosocomial infections: A qualitative study. Journal of
Hospital Infection, 102(4), 454-460. https://doi.org/10.1016/j.jhin.2018.08.013
Moynihan, R., Sanders, S., Michaleff, Z. A., Scott, A. M., Clark, J., To, E. J., Jones, M.,
Kitchener, E., Fox, M., Johansson, M., Lang, E., Duggan, A., Scott, I. &
Albarqouni, L. (2021). Impact of COVID-19 pandemic on utilization of
healthcare services: A systematic review. BMJ Open, 11(3), e045343.
https://doi.org/10.1136/bmjopen-2020-045343
Nayfeh, A., & Fowler, R. (2020). Understanding patient- and hospital-level factors
leading to differences, and disparities, in critical care. American Journal of
Respiratory and Critical Care Medicine, 201(6), 642-644.
https://doi.org/10.1164/rccm.202001-0116ed
Okuyama, J. H. H., Galvao, T. F., & Silva, M. T. (2018). Healthcare professional's
perception of patient safety measured by the hospital survey on patient safety
culture: A systematic review and meta-analysis. The Scientific World
Journal, 2018, 9156301. https://doi.org/10.1155/2018/9156301
Øversveen, E., Rydland, H. T., Bambra, C., & Eikemo, T. A. (2017). Rethinking the
relationship between socio-economic status and health: Making the case for
sociological theory in health inequality research. Scandinavian Journal of Public
Health, 45(2), 103-112.
Pengid, S., Peltzer, K., de Moura Villela, E. F., Fodjo, J. N. S., Siau, C. S., Chen, W. S.,
Bono, S. A., Jayasvasti, I., Hasan, M. T., Wanyenze, R. K., Hosseinipour, M. C.,
89
Dolo, H., Sessou, P., Ditekemena, J. D. & Colebunders, R. (2022). Using
Andersen’s model of health care utilization to assess factors associated with
COVID-19 testing among adults in nine low-and middle-income countries: An
online survey. BMC Health Services Research, 22(1).
https://doi.org/10.1186/s12913-022-07661-8
Popescu, I., Huckfeldt, P., Pane, J. D., & Escarce, J. J. (2019). Contributions of
geography and nongeographic factors to the White‐Black gap in hospital quality
for coronary heart disease: A decomposition analysis. Journal of the American
Heart Association, 8(23). https://doi.org/10.1161/jaha.119.011964
Price, P. C., Chiang, I. C. A., & Jhangiani, R. (2018). Research methods in psychology:
2
nd
Canadian edition.
Puni, A., & Hilton, S. (2020). Dimensions of authentic leadership and patient care
quality. Leadership in Health Services, 33(4), 365-383.
https://doi.org/10.1108/lhs-11-2019-0071
Rahman, M. S. (2020). The advantages and disadvantages of using qualitative and
quantitative approaches and methods in language “testing and assessment"
research: A literature review. Journal of Education and Learning, 6(1), 102-112.
https://doi.org/10.5539/jel.v6n1p102
Rath, M. (2020). Big data and IoT-allied challenges associated with healthcare
applications in smart and automated systems. In Data Analytics in Medicine:
Concepts, Methodologies, Tools, and Applications (pp. 1401-1414). IGI Global.

90
Rethy, L., Feinglass, J., Pool, L., Vu, T. H. T., & Kham S. S. (2019). Racial disparities in
heart failure hospitalizations and in-hospital mortality in Illinois: 2016- 2018.
Circulation, 140(1).
https://www.ahajournals.org/doi/10.1161/circ.140.suppl_1.16322
Rezaee, R., Rahimi, F., & Goli, A. (2021). Urban growth and urban need to fair
distribution of healthcare service: A case study on Shiraz metropolitan area. BMC
ResearchNnotes, 14(1), 1-6. https://doi.org/10.1186/s13104-021-05490-2
Rogers, J; Révész, A; (2020) Experimental and quasi-experimental
designs. In: McKinley, J and Rose, H, (eds.) The Routledge handbook of research
methods in applied linguistics. (pp. 133-143). Routledge: London, UK.
Ruiz-Pérez, I., Bermúdez-Tamayo, C., & Rodríguez-Barranco, M. (2017). Socio-
economic factors linked with mental health during the recession: A multilevel
analysis. International Journal for Equity in Health, 16(1), 1-8.
https://doi.org/10.1186/s12939-017-0518-x
Rupp, M. T. (2018). Assessing quality of care in pharmacy: Remembering Donabedian.
Journal of Managed Care & Specialty Pharmacy, 24(4), 354-356.
Illinois Department of Healthcare and Family Services. (2022). Y 2020 DSH MPA MHVA
Determination.
https://www2.illinois.gov/hfs/MedicalProviders/MedicaidReimbursement/Pages/
RY2020_DSH_MPA_MHVA_Determination.aspx.
Scholaske, L, Buss, C., Wadhwa. P., & Entringer, S. (2018). Maternal acculturation
potentiates the effect of low socio-economic status on birth weight in a cohort of

91
Mexican-American women in the US. The European Journal of Public Health.
28(1), 122-123. https://doi.org/10.1093/eurpub/cky048.033
Sibeudu, F. T., Uzochukwu, B. S., & Onwujekwe, O. E. (2017). Investigating socio-
economic inequity in access to and expenditures on routine immunization services
in Anambra state. BMC Research Notes, 10(1), 1-8.
https://doi.org/10.1186/s13104-017-2407-1
Silvestri, D., Goutos, D., Lloren, A., Zhou, S., Zhou, G., Farietta, T., Charania, S., Herrin,
J., Peltz, A., Lin, Z., & Bernheim, S. (2022). Factors associated with disparities in
hospital readmission rates among US adults dually eligible for Medicare and
Medicaid. JAMA Health Forum, 3(1), e214611.
https://doi.org/10.1001/jamahealthforum.2021.4611
Singh, A.S., & Masuku, M.B. (2014). Sampling techniques & determination of sample
size in applied statistics research: an overview. International Journal of
Economics, Commerce and Management, 2(11), 1-21. https://ijecm.co.uk/wp-
content/uploads/2014/11/21131.pdf.
Skagerström, J., Ericsson, C., Nilsen, P., Ekstedt, M., & Schildmeijer, K. (2017). Patient
involvement for improved patient safety: A qualitative study of nurses'
perceptions and experiences. Nursing Open, 4(4). https://doi.org./1002/nop.2.89.
Stockwell, D. C., Landrigan, C. P., Toomey, S. L., Westfall, M. Y., Liu, S., Parry, G.,
Coopersmith, A. S., Schuster, M. A., & GAPPS Study Group (2019). Racial,
ethnic, and socioeconomic disparities in patient safety events for hospitalized
children. Hospital Pediatrics, 9(1), 1–5. https://doi.org/10.1542/hpeds.2018-0131

92
Stoto, M. A., Woolverton, A., Kraemer, J., Barlow, P., & Clarke, M. (2022). COVID-19
data are messy: Analytic methods for rigorous impact analyses with imperfect
data. Globalization and Health, 18(1). https://doi.org/10.1186/s12992-021-00795-
0
Stratton, S. J. (2021). Population research: Convenience sampling strategies. Prehospital
and Disaster Medicine, 36(4), 373-374.
https://doi.org/10.1017/s1049023x21000649
Sun, J., Lyu, S., & Dai, Z. (2019). The impacts of socioeconomic status and lifestyle on
health status of residents: Evidence from Chinese general social survey data. The
International Journal of Health Planning and Management, 34(4), 1097-1108.
Taherdoost, H. (2016). Sampling methods in research methodology: How to choose a
sampling technique for research. https://hal.archives-ouvertes.fr/hal-
02546796/document.
Theofanidis, D., & Fountouki, A. (2018). Limitations and delimitations in the research
process. Perioperative Nursing, 7(3), 155-163.
Thompson, K. (2017). The strengths and limitations of secondary data.
https://revisesociology.com/2017/04/24/thestrengths-and-limitations-of-
secondary-data/
Travers, J. L., Hirschman, K. B., & Naylor, M. D. (2020). Adapting Andersen’s
expanded behavioral models of health services use to include older adults
receiving long-term services and supports. BMC Geriatrics, 20(1).
https://doi.org/10.1186/s12877-019-1405-7

93
Tuczyńska, M., Staszewski, R., Matthews-Kozanecka, M., & Baum, E. (2022). Impact of
socioeconomic status on the perception of accessibility to and quality of
healthcare services during the COVID-19 pandemic among poles—pilot
study. International Journal of Environmental Research and Public Health, 19(9),
5734. https://doi.org/10.3390/ijerph19095734
Tumin, D., Menegay, M., Shrider, E. A., Nau, M., & Tumin, R. (2018). Local income
inequality, individual socioeconomic status, and unmet healthcare needs in Ohio,
USA. Health Equity, 2(1), 37-44.
Unruh, L, & Hoffer, R. (2016), Predictors of gaps in patient safety and quality in US
hospitals. Health Services Research, 51(6), 2258-2281.
https://doi.org/10.1111.1475-6773.12468.
Van Hecke, A., Heinen, M., Fernåndez-Ortega, P., Graue, M., Hendriks, J. M., Høy, B.,
& Van Gaul, B. G. (2017). Systematic literature review on effectiveness of self-
management support interventions in patients with chronic conditions and low
socio-economic status. Journal of Advanced Nursing, 73(4), 775-793.
Vokes, R. A., Bearman, G., & Bazzoli, G. J. (2018). Hospital-acquired infections under
pay-for-performance systems: An administrative perspective on management and
change. Current Infectious Disease Reports, 20(9).
https://doi.org/10.1007/s11908-018-0638-5
Wang, J., & Geng, L. (2019). Effects of socioeconomic status on physical and
psychological health: Lifestyle as a mediator. International Journal of

94
Environmental Research and Public Health, 16(2), 281.
https://doi.org/10.3390/ijerph16020281
Wang, X., Chem J., Burström, B., & Burström, K. (2019). Exploring pathways to
outpatients' satisfaction with health care in Chinese public hospitals in urban and
rural areas using patient-reported experiences. International Journal for Equity in
Health, 18(1), 29. https://doi.org/10.1186/s12939-019-0932-3
Warchol, S. J., Monestime, J. P., Mayer, R. W., & Chien, W. W. (2019). Strategies to
reduce hospital readmission rates in a non-Medicaid-expansion state. Perspectives
in Health Information Management, 16(Summer), 1a.
Williams, D. R., Mohammed, S. A., Leavell, J., & Collins, C. (2010). Race,
socioeconomic status, and health: Complexities, ongoing challenges, and research
opportunities. Annals of the New York Academy of Sciences, 1186(1), 69-101.
https://doi.org/10.1111/j.1749-6632.2009.05339.x
Woodcock, T., Liberati, E. G., & Dixon-Woods. M. (2019). A mixed-methods study of
challenges experienced by clinical teams in measuring improvement. BMI Quality
and Safety, 1-10. https://doi.org/10.1136.bmjqs-2018-009048
World Health Organization. (2019). Patient safety. https://www.who.int/news-room/fact-
sheets/detail/patient-safety.
World Health Organization. (2021). The impact of COVID-19 on global health goals.
https://www.who.int/news-room/spotlight/the-impact-of-covid-19-on-global-
health-goals.

95
World Health Organization. (2021). Urban health. https://www.who.int/news-room/fact-
sheets/detail/urban-health.
Wylie, L., Corrado, A. M., Edwards, N., Benlamri, M., & Murcia Monroy, D. E. (2020).
Reframing resilience: Strengthening continuity of patient care to improve the
mental health of immigrants and refugees. International Journal of Mental Health
Nursing, 29(2), 171-176.
Wyskiel, R. M., Weeks, K., & Marstellcr, J. A. (2015). Inviting families to participate in
care: A family involvement menu. Joint Commission Journal on Quality and
Patient Safety, 43-46.
Yaya, S., Bishwajit, G., Ekholuenetale, M., Shah, V., Kadio, B., & Udenigwe, O. (2017).
Urban- rural difference in satisfaction with primary healthcare services in Ghana.
BMC Health Services Research, 17(1), 2017, 776. https://doi.org/10.1186/s12913-
017-2745-7
Yin, R. (2017). Case study research and applications: Design and methods. 6th Edition.
SAGE Publications.
Zhang, Y., Chen, Y., Wang, Y., Li, F., Pender, M., Wang, N., Yan, F., Ying, X., Tan, S.
& Fu, C. (2020). Reduction in healthcare services during the COVID-19
pandemic in China. BMJ Global Health, 5, 1-10. https://doi.org/10.1136/bmjgh-
2020-003421
Zhang, X., Dupre, M. E., Qiu, L., Zhou, W., Zhao, Y., & Gu, D. (2017). Urban-rural
differences in the association between access to healthcare and health outcomes
among older adults in China. BMC Geriatrics, 17(1), 1-11.

96
Zhang, Y., Khullar, D., Wang, F., Steel, P., Wu, Y., Orlander, D. Weiner, M., & Kaushal,
R. (2021) Socioeconomic variation in characteristics, outcomes, and healthcare
utilization of COVID-19 patients in New York City. PLoS ONE, 16(7): e0255171.
https://doi.org/10.1371/journal.pone.0255171

