


Introduction Interpersonal Psychological Safety In The United States Admissions To The
Hospital
In the United States, there are over 34 million admissions to the hospital with six million
individuals being admitted to the intensive care unit (ICU) each year (Kleinpell et al., 2019;
Statista, 2023). Governmental and regulatory agencies, including The Joint Commission (2008),
the Institute of Medicine (2010), and the World Health Organization, have mandated that
healthcare organizations mitigate patient errors, minimize fragmentation of care and costs, and
actively reform healthcare delivery (Almost et al., 2016; White & Griffith, 2019). Healthcare
organizations have responded by implementing interprofessional teams to manage and deliver
patient care (Bjurling-Sjöberg et al., 2017; Morgan et al., 2015).
The interprofessional team's composition can consist of any or all of the following
providers: advanced practice clinicians (APCs; i.e., includes advanced practice registered nurses
[APRNs] and physician assistants), physicians, registered nurses, therapists (physical,
occupation, and speech therapy), pharmacists, and case management nurses and social workers.
Nurse practitioners (NPs) are highly trained clinicians with two to three years of graduate-level
training, possess advanced degrees, and undergo rigorous preparation, licensure, and
credentialing processes before transitioning to clinical practice (Tracy & O’Grady, 2019). These
highly trained professionals are more than prepared to provide safe and effective care in the
interprofessional setting (Burrows et al., 2020; Institute of Medicine, 2010; Morgan et al., 2015;
Timmermans et al., 2017; Tracy & O’Grady, 2019; Winkleman et al., 2017).
The use of NPs as a member of the interprofessional team is an established care model in
the United States and has gained international popularity. Many healthcare organizations use
NPs as a part of the interprofessional team for several reasons, including increasing patient
complexity, the change in resident physician work hours, and the increasing availability of NPs

(Allen et al., 2019; Kleinpell et al., 2015). While the addition of NPs to the interprofessional care
team has many potential benefits, including decreasing provider workload and facilitating/
managing the coordination and continuity of care, the opportunity for an increase in
interprofessional conflict is also present, leading to the possibility of an unhealthy work
environment (Allen et al., 2019; Almost et al., 2016; Kleinpell et al., 2019). Interpersonal
conflict is a conflict between two or more individuals or parties and occurs when one's
perceptions and realities are discordant, ineffective, or inappropriate or miscommunication
occurs (Hocker & Wilmot, 2018; McCorkle & Reese, 2018). More importantly, the
consequences of interpersonal conflict necessitate healthcare organizations to have evidence-
based guidelines to manage and mitigate conflict.
Although researchers have studied personal factors contributing to conflict management
success in interprofessional teams, there are environmental factors that can facilitate effective
conflict management work (Almost et al., 2016; Edmondson, 1999, 2019). Psychological safety
is an environmental factor that influences how individuals handle or respond to interpersonal
conflict. Individuals who feel psychologically safe are thought to handle conflict better.
Psychological safety is a shared belief that team members can be open, candid, and honest with
each other without fear of reprisal or retribution (Edmondson, 1999, 2019). However, an
individual's interpersonal conflict management style has not been studied in the context of
environmental factors such as psychological safety.
Knowledge generated by this study provides additional insight and understanding of
psychological safety and interpersonal conflict management style utilized by NPs to manage
conflict that emerges from being a part of an interprofessional team. Understanding the
association between psychological safety and interpersonal conflict management style helps

organizations and leaders build an organizational culture that fosters collegiality and
collaboration, creating an environment where effective conflict management work can occur
(Almost et al., 2016). This chapter begins with a description of the statement of the problem,
followed by the purpose of the study and research questions. Next, the significance of the study
is described, followed by the conceptual framework. Definitions of key terms provide additional
clarity of obscure or unconventional terms.
Statement of the Problem
In the United States, interprofessional teams in healthcare organizations are becoming
more common. NPs play a pivotal role as interprofessional healthcare team members. However,
their addition to the team has led to an increase in interpersonal conflict with other healthcare
professionals (Aberese-Ako et al., 2015; Avgar & Neuman, 2015; Del Pino-Jones et al., 2019;
Donald et al., 2015; Ervin et al., 2018; Glymph et al., 2015; Kim et al., 2017; Rowland, 2017;
Stadick, 2020). NPs receive variable degrees of training in conflict management during their
professional education and enter the workforce with differing degrees of communication and
interpersonal problem-solving skills, which can impact their ability to navigate and manage
interpersonal conflict (Cochran et al., 2018; Field et al., 2014; Moeller & Kwantes, 2015; Samuel
et al., 2015). The American Association of Colleges of Nursing (2021) and the Accreditation
Council for Graduate Medical Education (2005, 2018) strongly encourage educational programs
to provide interprofessional care training, including effective communication and conflict
management.
When conflict is ineffective or inappropriately managed, patient care is jeopardized,
leading to increased medical errors and decreased patient satisfaction, increased financial and
litigation risk, patient harm, and even death (Avgar & Neuman, 2015; Glymph et al., 2015;

Rowland, 2017). Approximately 490,000 deaths are attributed annually to poor communication
and interpersonal conflict (Vogus & Iacobucci, 2016). Although researchers have studied
personal factors contributing to successful conflict management (e.g., effective communication,
collaboration, and emotional intelligence), environmental factors, such as psychological safety,
can facilitate appropriate conflict management success (Edmondson, 1999, 2019; Tekleab et al.,
2009). Psychological safety is a critical environmental factor influencing interprofessional teams
and conflict management (Edmondson, 1999, 2019). Based on the literature findings, research is
needed about environmental factors like psychological safety in the context of conflict
management style and perceived conflict management success among NPs working in an
interprofessional acute or critical care team.
Purpose of the Study
This quantitative correlational study aimed to understand differences in perceived
psychological safety associated with conflict management style and theorize how perceived
psychological safety predicts perceived conflict management success among NPs working in an
interprofessional acute or critical care team in the United States. While previous research
regarding conflict management and the impact of psychological safety exists, there is a paucity
of literature regarding how psychological safety, in the context of conflict management styles
and perceived conflict management success, among NPs occurs.
Several scales were used to measure the variables. Psychological safety was measured by
Edmondson's Psychological Safety Survey subscale (PSS; Edmondson, 1999), and
interprofessional conflict management style was measured by Rahim's (1983) Organizational
Conflict Inventory-II (ROCI-II). Tekleab et al.'s (2009) Team Conflict and Conflict Management

survey, specifically the Conflict Management Success subscale (CMS), measured team conflict
management success. The three variables were analyzed as interval levels of measurement.
Three primary constructs, conflict management style (Blake & Mouton, 1964; Rahim,
1983; Thomas & Kilmann, 1974), psychological safety (Edmondson, 1999), and team conflict
management success (Tekleab et al., 2009), guide the study. Participants include NPs working in
the United States who are members of an interprofessional team caring for acute or critically ill
individuals. Surveys were sent electronically to eligible participants. Data collection consisted of
a multi-item questionnaire containing demographic questions (e.g., years of professional
experience, geographic location, gender, ethnicity, profession, etc.) and Rahim's (1983) ROCI-II,
Edmondson's (1999) PSS, and Tekleab et al.'s (2009) CMS instruments.
Research Questions
RQ1. How do scores for perceived psychological safety differ based on interpersonal
conflict management style among NPs working in interprofessional acute care or critical care
teams in the United States?
H10. There are no statistically significant differences in perceived psychological safety
among NPs based on their conflict management style.
H1a. There are statistically significant differences in perceived psychological safety
among NPs based on their conflict management style, with NPs utilizing an integrating or
collaborating style of conflict management having higher levels of perceived psychological
safety than NPs who use other conflict management styles.
RQ2. How does psychological safety predict perceived conflict management success
among NPs working in interprofessional acute care or critical care teams in the United States?

H20. Psychological safety is not a statistically significant predictor of NPs' perceived
conflict management success.
H2a. Psychological safety is a statistically significant predictor of NPs' perceived conflict
management success, with higher levels of psychological safety predicting higher levels of
perceived conflict management success.
Definition of Key Terms
To assist with clarity and to facilitate understanding, the following key terms are defined:
Advanced practice clinician (APC). Advanced practice clinician is an overarching
terms to describe an advanced-level care provider, such as an Advanced Practice Registered
Nurse (APRN; e.g., NP or Physician Assistant [PA-C]).
Advanced practice registered nurse (APRN). Advanced practice registered nurses are
registered nurses who are educated at the graduate level (masters, doctoral, or postgraduate
degree) and include NPs, clinical nurse specialists (CNS), certified nurse-midwives (CNM), and
certified registered nurse anesthetists (CRNA; Hamric et al., 2014). APRNs diagnose illness,
develop, implement, and evaluate treatment plans, prescribe medications, and manage acute,
chronic, and complex health issues. APRNs undergo rigorous, evidence-based licensure
examinations, maintain national certification in their APRN role, complete continuing education,
and are licensed and regulated by state boards of nursing (Hamric et al., 2014).
Conflict. Conflict is the expressed struggle between two or more interdependent parts
who perceive incompatible goals, scarce resources, and interference, which prevents the
achievement of goals or outcomes (Hocker & Wilmot, 2018; McCorkle & Reese, 2018; Putnam,
2013).

Conflict competence. Conflict competence is one's ability to recognize and appropriately
manage conflict using positive psychology skills, such as cognitive, emotional intelligence (EI),
and behavioral skills, to seek a productive resolution of the issue while minimizing escalation or
harm (Avgar & Neuman, 2015; Hocker & Wilmot, 2018; McCorkle & Reese, 2018).
Conflict management styles. Individuals manage interpersonal conflict through one of
five different styles, including avoiding, dominating (competing), obliging (accommodating),
compromising, and integrating (collaborating; Hocker & Wilmot, 2018; Rahim, 2011).
Conflict management success. Conflict management success is defined as a team's
ability to work through conflict and maintain a cohesive state where the group members can
achieve the team's goals or outcomes (Tekleab et al., 2009).
Interpersonal conflict. Interpersonal conflict is a conflict between two or more
individuals or parties and occurs when one's perceptions and realities are discordant, ineffective,
or inappropriate or miscommunication occurs (Hocker & Wilmot, 2018; McCorkle & Reese,
2018).
Interprofessional care. Interprofessional care is defined as a multidisciplinary
collaborative approach to patient-centered care. Unlike the traditional hierarchical approach to
healthcare, interprofessional care encourages each discipline (i.e., medicine, nursing, pharmacy,
allied health, physical/occupational/speech therapy, case management) to practice at the highest
level (Bjurling-Sjöberg et al., 2017; Institute of Medicine, 2010).
Interprofessional teams. An interprofessional team is a multidisciplinary healthcare
team that can consist of any or all of the following providers: APCs, physicians, registered
nurses, nonlicensed aides, therapists (physical, occupational, and speech therapy and aides),
pharmacists, and case management nurses and social workers (Institute of Medicine, 2010).

Perception. Perception is how individuals, groups, or organizations interpret verbal and
nonverbal messages from others (Hocker & Wilmot, 2018).
Physician assistants (PA-C). PA-Cs are medical professionals similar to APRNs who
diagnose illness, develop, implement, and evaluate treatment plans, prescribe medications, and
assist in surgery. PA-Cs are graduate-prepared and complete over 2000 clinical hours in medical
and surgical science (traditional medical model, similar to physicians). They undergo a rigorous
certification process, including passing a national certification exam, and must recertify every ten
years through a comprehensive examination covering general medical knowledge. These
individuals practice in every state and are regulated by state medical boards (American Academy
of Physician Assistants, n.d.).
Power. Power is defined as the ability to produce intended effects or outcomes by
influencing others or resisting the influence of others (Hocker & Wilmot, 2018).
Psychological safety. Psychological safety is "a team-level phenomenon where all team
members believe they are safe to take interpersonal risks" (Edmondson, 1999, p. 354).
Team cohesion. Team cohesion is the shared connection of team members that fosters a
willingness to stay together and work toward accomplishing team goals (Casey-Campbell &
Martens, 2009).
Summary
This chapter examines the dynamic nature of the interpersonal conflict that emerges in
the healthcare setting, particularly the degree of perceived psychological safety and the style of
management NPs use to manage interpersonal conflict when functioning as interprofessional
team members. The problem and purpose statements and the research questions and hypotheses
provide insight into the proposed study's overall approach and guidance. A brief introduction of

the study's methodology and proposed instruments are explored. Key terms and definitions are
provided to clarify terms that are not commonly used or understood. Chapter 2 thoroughly
reviews seminal and current literature on the history and role of APRNs, particularly NPs,
conflict and conflict management in the workplace, communication, conflict management
success, and psychological safety.

Chapter 2: Literature Review
When interpersonal conflict among members of healthcare teams is inadequately or
inappropriately addressed, the consequences can be devastating for patients, clinicians, and
organizations. Despite the high stakes associated with healthcare delivery and the potential for
error, many healthcare providers, including NPs, receive little to no formal conflict management
training. Many healthcare providers enter the workforce with highly variable differences in
interpersonal communication skills (Cochran et al., 2018). Variability in preparation creates
challenges for healthcare organizations and leaders who must ensure that every healthcare team
member can effectively manage conflict. While the impact of ineffective or poorly managed
conflict is widely understood, little is known about the personal and environmental factors that
impact the ability of NPs to manage conflict effectively.
The purpose of this quantitative correlational study was to investigate if there were
differences in perceived psychological safety associated with conflict management style and to
evaluate how perceived psychological safety is associated with perceived conflict management
success among NPs working in an interprofessional acute or critical care team in the United
States. In this chapter, I describe the literature review process, theoretical frameworks supporting
and guiding this study, and the historical and salient literature about interpersonal conflict and
interprofessional care, including conflict management success and psychological safety.
Literature Search Methods
A comprehensive literature search was conducted to identify literature relevant to the
research questions and study context. The One Search database from the Abilene Christian
University’s Brown Library is the principal retrieval source. Within the One Search database, I
primarily concentrated my searches on the following databases: EBSCOhost, CINAHL, ERIC,

and Science Direct. Aside from the seminal articles which provide background and theoretical
support and study reinforcement, the following parameters were put in place: (a) publication
years 2000–2023, (b) peer-reviewed academic journals, (c) full-text complete articles, and (d)
geographic restriction of the United States, Canada, Europe, and Australia. Search phrases and
key terms included communication, communication competence, communication theories,
conflict, conflict management, interprofessional care, interprofessional collaboration,
interprofessional teams, conflict interpersonal conflict, group dynamics, healthcare,
psychological safety, perception, problem-solving, qualitative methodology, quantitative
methodology, self-efficacy, teamwork, and transition are used for additional stratification and
clarity. Boolean operators and truncation were used, and combinations of keywords were used to
locate a broad range of articles.
Theoretical Framework Discussion
Social Cognitive Theory
Albert Bandura's (1986) social cognitive theory (SCT) serves as the primary theoretical
framework for this study. The theory was initially known as the social learning theory. The SCT
is based on the previous works by Holt and Brown (1931) and Miller and Dollard (1941), which
postulates that social learning and interaction are reaffirmed by positive reinforcement and
motivation. Ongoing research led Bandura to expand and rename his theory in 1986 to
emphasize that personal, behavioral, and environmental influences heavily influence human
behavior. In essence, Bandura (1977, 1986) argued that individuals learn through dynamic and
static means, including observing others and interacting with other individuals and the
environment. As a result, a reciprocal triadic relationship exists between one's environment,
behavior, and cognition. The SCT is an agentic theory that argues that individuals are self-

developing, self-regulating, self-reflecting, and proactive. Furthermore, humans are
psychologically and physiologically advanced beings who possess intentionality, forethought,
self-reactiveness, and are self-reflective (Bandura, 1986).
Application of SCT to the Study
Interprofessional teams are composed of individuals with convergent and divergent
backgrounds coming together to assess, manage, and care for the sick and injured. Individuals
respond to conflict in either a constructive or destructive manner and engage in defensive or
supportive communication and behavioral processes (Gibb, 1961; Hocker & Wilmot, 2018;
McCorkle & Reese, 2018; Moeller & Kwantes, 2015). Effective interprofessional teams
recognize the value each member brings to the group. Individuals, especially members of
complex teams, such as interprofessional healthcare teams, function best when communication is
open and honest, members respect and trust each other and are comfortable being themselves
(O'Leary, 2016). Members of the interprofessional team engage with each other and the team.
Individual behavior of team members is impacted by intrapersonal factors, including conflict
management style and their environment, including the psychological safety of their team. The
synergy between personal and environmental factors impacts their care delivery, positively
impacting patients through improved patient outcomes, improved patient and provider
satisfaction, decreased care costs and duplication of resources, and reduced errors.
Sources of conflict in healthcare, in particular nursing, have been attributed to
organizational factors such as poor work environment (role ambiguity), interpersonal factors
(poor communication), or individual characteristics (low emotional intelligence; Almost et al.,
2016). Dysfunctional and ineffective teams do not acknowledge the individual’s individual and
collective worth, fail to communicate effectively, and act unprofessionally. The lack of

synergism and collaboration negatively impacts the patient and provider by increasing the cost of
care and increased utilization of resources, decreasing the team members' psychological safety,
and increasing the chance of errors occurring (Bjurling-Sjöberg et al., 2016; Ervin et al., 2018;
Stadick, 2020). Moreover, teams in acute and critical care settings operate in a low temporal
stability environment, increasing conflict opportunities (Alexanian et al., 2015; Andreatta, 2010;
Hughes et al., 2016).
Literature Review
NP
Overview of the NP Profession. The profession of nursing, in particular advanced
practice nursing, has evolved over the last 135 years due to societal needs and organizational
demands. Advanced practice includes the roles of certified registered nurse anesthesia (CRNA),
certified nurse midwife (CNM), certified clinical nurse specialist (CNS), and certified nurse
practitioner (CNP). Each role has a particular focus but shares nursing as a core discipline. From
the work by Lillian Wald (Henry Street Settlement House in New York City) in the late 1800s to
the Frontier Nursing Service established by Mary Breckinridge in 1928 to care for individuals
living in Appalachia to the modern-day advanced practice movement, nurses continue to answer
the call of society through innovative and frontline care.
The modern NP role emerged in the 1960s due to the continued need for accessible,
comprehensive, affordable healthcare. Loretta Ford, a registered nurse, and Henry Silver, a
physician at the University of Colorado, recognized the need for pediatric providers to manage
well-child visits and common medical issues. Ford and Silver implemented a demonstration
project funded by the Commonwealth Foundation to prepare registered nurses to fill the void left
by physicians seeking specialty and subspecialty roles. A study by Ford and Silver (1967)

demonstrated that these highly trained nurses, termed pediatric nurse practitioners (PNP), could
manage most well and ill children in the community health setting while increasing access to
private pediatricians by 33%.
The PNP role established the precedent for other NP specialties. In the 1980s, additional
focus areas for NPs developed, including family, women's health, and neonatal specializations.
NPs and their supporters convinced legislatures nationwide to pass laws and establish policies to
support their ongoing practice. During this time, the academic preparation of NPs transitioned
from certificate to master's degree. Many states implemented or revised their advanced nursing
scope of practice, allowing NPs greater authority and autonomy.
The number of NPs grew in the 1990s as physicians pursued specialties outside of
primary care. The adult-gerontology acute care nurse practitioner (AGACNP) role was created
partly due to the increasing number of residency shortages, especially in critical care. The role of
the acute care nurse practitioner (ACNP), the predecessor of the AGACNP, continued to evolve
in the late 1990s due to increased patient acuity, decreased number of physicians, and a shortage
of critical care intensivists. The number of graduate-level nurse practitioner programs continues
to grow in response to the increased demand for training and preparation. Over the last 15 to 20
years, the field of advanced practice nursing has continued to grow with academic preparation
shifting from master’s to doctoral preparation.
Throughout the 20th and first part of the 21st century, APRNs, in particular NPs, continue
to meet the needs of individuals, especially those who are underserved, lack funding, or live in
rural America. The role provides an opportunity for advanced-prepared nurses to significantly
impact patient outcomes at a dynamic time in the history of healthcare delivery. However, their

impact is often limited by their scope of practice and how others on the team, namely physicians,
view their contribution.
Nurse Practitioner Scope of Practice. The scope of practice for APRNs is determined
by national, state, local, organizational, and personal influences. In 2004, the American
Association of Colleges of Nursing advanced the concept of APRNs having a doctoral degree as
their terminal degree and, more importantly, the concept of APRNs working to the fullest extent
of their licensure. To continue to meet the needs of individuals and ensure patient safety and
practical outcomes, the licensure, accreditation, certification, and education (LACE) guidelines
and consensus statement were initiated. Endorsed by all major nursing organizations, the LACE
guidelines and consensus statement aim to regulate advanced practice by ensuring the four roles
— CRNA, CNM, CNS, and CNP and the six populations of focus —family (individual life
span), adult-gerontology, pediatrics, neonatal, women’s health, and psych/mental health are
providing appropriate levels of care (Tracy & O'Grady, 2019).
APRNs, particularly NPs, are currently prepared at the master’s or doctoral level with
training and education focused on advanced nursing science and clinical preparation. In addition,
APRNs possess advanced national certification and licensure. APRNs, in particular, are unique
as they do not practice medicine. Instead, APRNs practice advanced nursing by evaluating,
managing, and treating individuals with acute and chronic issues on a wellness-illness continuum
using a dynamic assessment, diagnosis, implementation, and evaluation process in primary and
tertiary settings. NPs are prepared to practice as primary or acute care NPs.
Despite the extensive preparation NPs and other healthcare providers undergo during
their professional development, they often lack formal preparation in communication,
collaboration, and conflict management. Ironically, the core competencies for doctoral

preparation include teamwork, communication, and conflict management skills in their domains.
However, many schools fail to prepare NPs in this area adequately. While the presence or
inclusion of nurses with expertise, including NPs, facilitates improved access to care and, with
time, facilitates communication, interprofessional healthcare team members learn and work
together via on-the-job training (Burtscher et al., 2020).
The NP’s Role in Interprofessional Teams. Healthcare in the United States is becoming
increasingly more complex, expensive, and time-intensive due to increased longevity of life,
industrialization of society, lifestyle choices, and acute and chronic disease processes. The need
for qualified providers has never been greater; the demand for healthcare providers outweighs
the available supply due to the shifting landscape. Fewer physicians are completing advanced
residencies and fellowships, and this trend is expected over the next several decades.
Furthermore, government and regulatory agencies, including The Joint Commission (2008), the
Institute of Medicine (2010), and the World Health Organization, mandate that healthcare
organizations mitigate patient errors, minimize fragmentation of care and costs, and actively
reform healthcare. As a result, healthcare organizations must ensure that individuals are
adequately cared for by implementing creative, cost-effective, and effective strategies, including
interprofessional care (Burtscher et al., 2020; Dillon et al., 2016; Johal & Dodd, 2017).
Many healthcare organizations have elected to use interprofessional teams to manage
patient care collaboratively. Interprofessional care is a partnership between individuals from
diverse backgrounds and professional cultures who work together to solve problems or provide
services. Effective interprofessional care is associated with better service delivery and patient
outcomes (Morgan et al., 2015; Stadick, 2020).

In the United States, the interprofessional team's composition varies among organizations
depending on their size and focus. The team comprises physicians, advanced practice clinicians
(e.g., nurse practitioners and physician assistants), nursing, allied health (e.g., physical,
occupational, and speech therapy), pharmacy, and case management/social services. Teaching
facilities often include various learners, including medical, advanced practice clinicians,
pharmacy students, and physicians completing residencies and fellowships. Nurse practitioners
are highly trained healthcare providers with two to three years of graduate-level training, possess
advanced degrees, and undergo rigorous preparation, licensure, and credentialing before
transitioning to clinical practice (Del Pino-Jones et al., 2019).
While nurse practitioners may lack the confidence for independent practice after
completing their initial training program, they are more than adequately prepared to provide safe
and effective care in the collaborative setting (Burrows et al., 2020; Institute of Medicine, 2010;
Morgan et al., 2015; Timmermans et al., 2017; Winkleman et al., 2017). Moreover, there are
enormous benefits to this. For example, in a small mixed methods study, researchers examined
the perceptions of attending-level physicians on having nurse practitioners function as a member
of the interprofessional team (Del Pino-Jones et al., 2019). The respondents reported that nurse
practitioners reduced the physician's workload and improved communication and provider
satisfaction. Del Pino-Jones et al. (2019) concluded that adding nurse practitioners to the
treatment team financially benefited the organization. They often function at the senior resident's
rank and can manage an appropriately sized patient panel, allowing improved access to care. In
another study, utilizing NPs as a part of the interprofessional team provided several key benefits
to patients and teams: enhancing the quality of care, clinical outcomes, and patient safety. It also
decreased the average length of patients’ stay, increased providers’ adherence to evidence-based

treatment, and increased organizational productivity by enhancing clinical training opportunities
(Kleinpell et al., 2020). A cross-sectional quantitative study of 579 hospitals across the United
States with three or more NPs per 100 beds found lower 30-day mortality [OR = 0.76; 95% CI =
0.67-0.82; p < .001], lower 7-day readmissions rate [OR = 0.90; 95% CI = 0.96-0.96; p < .001),
decreased length of stay (incident rate ratio = 0.92; 95% CI = 0.88-0.96; p < .001) and a 5.4%
lower average cost of care [95% CI= 3.8%-7.1%] compared to facilities with one or less NPs per
100 beds. The authors (Aiken et al., 2021) also found that patients and nurses in hospitals with
higher NP/bed ratios were more likely to report better care quality, safety, and higher job
satisfaction, leading to greater intention to stay and lower nurses' burnout.
Interprofessional teamwork contributes to safe and efficient patient care, particularly in
the acute and critical care setting. Effective team performance is contingent upon managing the
6Cs: conflict, cooperation, coordination, coaching, communication, and cognition (Ervin et al.,
2018; Salas, Shuffler, et al., 2015). Effective interprofessional collaboration requires strong
communication skills and is essential to teamwork. However, using nurse practitioners as part of
the interprofessional care team model has several challenges, including the perceived expense of
recruiting, onboarding, and training NPs. Additionally, physicians' perceptions of NPs remain
variable depending, in part, on the physicians' exposure and comfort working with NPs.
Specifically, challenges include resistance to interprofessional practice models, concern
regarding conflict with house staff and other trainees, and the difficulty obtaining accurate data
regarding APRN contributions to the team and organization (Kleinpell et al., 2020).
Conflict in the Workplace
Researchers recognize the need to study conflict management in intensive care unit (ICU)
teams. According to Cronin and Weinberg (2007) and Weingart et al. (2015), future work on

ICU teams should examine the sources of conflict, as well as the frequency, intensity, and
expression of different types of conflict to determine more effective ways of addressing and
managing conflict. For this study, conflict is viewed as the expressed struggle between two or
more interdependent individuals who perceive incompatible goals, scarce resources, and
interference, which prevents the achievement of goals or outcomes (Hocker & Wilmot, 2018;
McCorkle & Reese, 2018).
Conflict has been categorized and mainly studied in terms of conflict types, conflict
management styles, and constructive and destructive organizational outcomes (Bohlander &
Snell, 2010; Robbins, 1978; Van de Vliert & Euwema, 1994). Conflict in the workplace is often
characterized by disruptive behaviors ranging from incivility to sexual misconduct (Bae et al.,
2020; Hastie et al., 2020). Each clinician possesses diverse knowledge acquired through different
training pathways in various healthcare settings. These differences can improve the quality of
care for patients but can also lead to ineffective interprofessional interactions and conflict among
providers (Bae et al., 2020). Interprofessional conflicts tend to be multi-factorial, making them
difficult to solve, and significantly, unresolved conflict can impede open exchanges of
information and reduce appreciation of one another’s expertise (Bajwa et al., 2020; Bochatay et
al., 2017; Boustras & Tokakis, 2018; Kayser & Kaplan, 2020; Kim et al., 2017).
Since 2008, The Joint Commission, the primary healthcare accrediting agency in the
United States, has required agencies to have policies and procedures to address, manage, and
mitigate the consequences of inappropriate behavior and unresolved conflict (Hastie et al., 2020;
Kim et al., 2017; The Joint Commission, 2008). Hospitals and healthcare organizations must
develop codes of conduct, define behavior norms, and enforce consequences for violating
standards. Similarly, the American Association of Colleges of Nursing (2021) and the

Accreditation Council for Graduate Medical Education (2005, 2018) encourage schools and
training programs to provide valuable and practical conflict management training. However,
educational programs have historically done little to help equip students to effectively manage
conflict (Broukhim et al., 2019). Therefore, healthcare providers often lack the knowledge to
manage conflict, perceive inadequate institutional support, or display reluctance to enforce
consequences for rule violations (Bajwa et al., 2020).
Sources of Workplace Conflict
Workplace conflict is often categorized as intrapersonal, interpersonal, and
organizational. While each of these is important in the workplace's conflict management, this
study is concerned with interpersonal conflict management in the context of interprofessional
teams. Three primary types of workplace conflict are pertinent to the interprofessional team:
task, relationship, and process. Task conflict emerges when differing views and disagreements
among team members emerge. The dispute often centers around the specifics and outcomes of
the task. On the other hand, relationship conflict arises when there are unresolved individual
differences, goals, or issues of the individuals involved unrelated to the functions being
performed. Finally, process conflict occurs when goals, resources, disagreements, or issues
around the task emerge (Hocker & Wilmot, 2018; McCorkle & Reese, 2018).
As the proposed study is based on interprofessional teams, this section's primary focus
will be interpersonal conflict. However, it is vital to understand intrapersonal and organizational
sources of conflict to appreciate the complexity of interpersonal conflict.
Intrapersonal Sources of Workplace Conflict. Conflict, in particular, interpersonal
conflict, typically evolves through a process of four phases: (a) the stimulus or inciting event
(perceived or actual), (b) frustration by one or more parties, (c) identification of the cause, and

(d) expression of behaviors in response to the cause/source, leading to an outcome (Almost et al.,
2016; Budd et al., 2020; Saltman et al., 2006). The ability to effectively engage and interact with
others is predicated on individual characteristics and personality traits, including an individual’s
core beliefs, motives, attitudes, values, and knowledge (Almost et al., 2016).
Individuals develop coping mechanisms and strategies for challenging situations
(McCorkle & Reese, 2018; Rahim, 2002). In addition, the degree of an individual’s emotional
intelligence either helps or hinders their ability to manage conflict. Emotional intelligence is
one’s ability to effectively perceive and manage emotions to interact with oneself and others
(Almost et al., 2016). Research shows that personality and emotional traits are antecedents to
effective conflict management (Almost et al., 2016). Lack of emotional intelligence and
personality traits can negatively impact conflict management (Almost et al., 2016). One’s
emotions and mood can affect conflict mitigation as emotions and mood influence decision-
making. The behaviors that emerge based on one’s negative emotions and moods can facilitate
the escalation of conflict (Budd et al., 2020; Kim et al., 2016, 2017).
An individual’s physical and mental/emotional health, including their personality traits
and the degree of emotional intelligence, impacts their ability to process and manage conflict.
One of the most difficult challenges in handling conflict is managing the affective (emotional)
reactions and moods that emerge when conflict occurs (Almost et al., 2016; Budd et al., 2020).
An individual’s ability to effectively manage conflict is impacted when their psychogenic
emotions are involved. Conflict can often magnify these differences, as no two conflicts or
individuals are alike. Likewise, one's emotional state often impacts cognitive dissonance and
cognitive functioning. One way to better understand how an individual approaches
disagreements and conflict is through the lens of emotional intelligence. Research supports that

personality and emotions are antecedents to one’s ability to manage conflict effectively, and
one’s level of emotional intelligence influences the decision to engage or avoid conflict (Budd et
al., 2020).
According to an integrated literature review by Almost et al. (2016) and an empirical
study by Budd et al. (2020), individuals who are highly neurotic are more likely to report
instances of workplace conflict and less likely to use integrating or collaborating style of conflict
management. In addition, the authors noted that individuals who are neurotic were less able to
control emotions and typically have less social support structure. At the same time, highly
extroverted individuals were also more likely to report instances of workplace conflict but less
likely to use avoiding styles of conflict management. The authors also noted that extroverted
individuals may express assertiveness and tend to be more forceful in communicating opinions.
Conversely, highly conscientious individuals were less likely to report workplace conflict and
more likely to use an integrating or collaborative conflict management style. Also, conscientious
individuals are more likely to have greater impulse control and determination, resulting in less
conflict. These findings align with Rahim’s (2002) earlier work, which found that a person’s
attitude and beliefs that are prominent in directing their behavior may be countercurrent to those
helped by others in the conflict, leading to additional stress and challenges, especially at the
organizational level.
Organizational Sources of Workplace Conflict. In the workplace, conflict may arise
when employees have different behavior preferences regarding their joint actions or are
independent in performing a function or activity when working together (Rahim, 2002). Conflict
is a dynamic and interactive process that manifests when an actual or perceived incompatibility
or disagreement emerges (Rahim, 2002). In acute and critical care healthcare settings,

organizational sources of conflict often occur as barriers to practice, including role ambiguity,
scope of practice, workload, and distribution of resources (Fealy et al., 2018).
Nurse practitioners are often constrained in their ability to practice to the full extent of
their education and training, and these constraints exist as regulatory, institutional, and cultural
barriers. Left unaddressed, these barriers can lead to conflict. Regulating barriers restricting the
scope of practice occurs primarily at the state level. However, a practitioner may have credentials
to perform a specific diagnosis and therapeutic procedures. Local hospitals and organizational
by-laws typically govern the credentialing and privileging process. Bylaws can vary from one
hospital to another, and NPs may not be able to obtain clinical privileges at each hospital. In
addition, the scope of practice regulation also exists at the state and federal legislation level,
which may prevent individuals from full practice. Scope of practice issues include role
expansion, boundaries, clinical jurisdiction, and professional regulation (Fealy et al., 2018).
Lack of clarity can lead to role ambiguity and create organizational conflict (Almost et
al., 2016). Role ambiguity often stems from differences in how NPs and other healthcare
providers, such as physicians, are educated and trained. Unlike physicians and PA-Cs, prepared
using the medical model with a biomedical approach, NPs are trained using nursing science as
the foundation for advanced practice. Advanced practice nursing is multifaceted, and while there
are similarities to the medical model (i.e., the inclusion of a biomedical approach), nursing
science also includes additional spheres of personal health, environment, and nursing. Heale and
Rieck-Buckley (2015) identified a general lack of understanding of the APRN role and
disparities in the various roles and healthcare settings as barriers to effective practice.
The modern healthcare community in the United States has endorsed the continued
evolution of the NP role, evidenced by the Institute of Medicine's (2010) support that nurses

should practice at the fullest extent of their professional education and training and barriers to
full scope of practice should be removed. Obstacles at the organizational level include full scope
and legislative limitations, lack of regulation of roles, lack of title protection, and low nursing
representation in policy development (Heale & Rieck-Buckley, 2015). Additional barriers
include team processes, teamwork environment, environmental awareness, leadership, shared
understanding, decision-making, communication, and team role knowledge (Kilpatrick et al.,
2020). Likewise, barriers such as resource allocation and constraints, including time,
composition, staffing, and financial challenges, healthcare professionals had to negotiate under
pressure while delivering care in high patient and complex environments (Kim et al., 2016).
Additional aspects of professional practice leading to organizational conflict include
workflow, resource allocation, and reporting structure. The NP may report through the
Department of Nursing or Medical Staff Services, while physicians and PA-Cs typically report
through Medical Staff Services. How individuals report can cause conflict, as there can be a lack
of consistent goals and poor communication (Kim et al., 2016). While several states allow NPs to
practice independently with full practice authority for NPs, PA-Cs continue to have a supervisory
relationship with the physicians they work as they have a different supervising structure
(Sarzynski & Barry, 2019). Furthermore, although some states allow NPs to practice
unsupervised, NPs often collaborate with physicians to provide care in critical care and higher
acuity settings. This collaboration is often mandated by the healthcare organization where the
care is provided, regardless of state practice laws.
Internally, organizational conflict emerges when there is a perceived or actual imbalance
in the workload or distribution of resources (Kim et al., 2016). Imbalance often leads to an
increased resistance to change, which in turn leads to decreased organizational commitment and

productivity. While there is a dearth of empirical studies examining workload imbalance and the
NP specifically, evidence supports the notion that an imbalance in workload leads to conflict. In
an integrative literature review by Ervin et al. (2018), ICU teams were noted to have low
temporal stability, with team members often changing, as residents, learners, and attending
providers rotate onto and off service continuously. Wildman et al. (2012) noted that a patient in
the critical care unit may spend upward of two weeks or more in the ICU and have many
different providers managing their care. Nurses, including APRNs, are central members of the
ICU team because they are directly involved in all of the care, including directing, managing,
coordinating, and delivering care (Ervin et al., 2018). As a result, registered and advanced
practice nurses (NPs) must manage a significant workload. Unaddressed organizational conflict
resulting from unbalanced workloads can contribute to absenteeism, higher employee turnover,
and additional expenses related to recruiting and onboarding new hires (Aberese-Ako et al.,
2015; Kim et al., 2016).
From an organizational perspective, research suggests collaborative behaviors lead to
collaborative conflict management (Kim et al., 2017; McKibben, 2017). On the other hand,
organizational cultures that encourage dominating or avoiding behaviors are considered less
effective and lead to poor morale, mistrust, poor communication, and less collaborative or
synergistic behavior. This collective lack of unity leads to insufficient information exchange and
allows for patient harm or clinician burnout (Zhao et al., 2021). More importantly, the
nationwide focus of Triple Aim (e.g., focusing on better care, improved quality for individuals
and populations, and lower cost) is achieved through collaboration and effective communication,
which are the foundations of effective conflict management (Mery et al., 2017).

The acute and critical care setting can also be a significant source of conflict due to the
high stress and fast pace of care required. The workflow in the critical care setting is often
unpredictable due to the inherent nature of the care provided (Ervin et al., 2018). Higher conflict
reports were found in environments with intolerable temperatures, poor lighting and air quality,
and significant noise (Ervin et al., 2018). Additionally, in the critical care setting, the lack of
time for meetings, problems with decision-making, and lack of consistent goals and ongoing
changes not being communicated are antecedents for conflict development (Ervin et al., 2018;
Kim et al., 2016).
Interpersonal Sources of Workplace Conflict. Challenges and barriers to the effective
implementation of interprofessional care teams include traditional hierarchy and power
differentials, the various backgrounds and diversity of team members, and previous experience
working with teams. The use of different decision-making pathways, distrust of other
professional's competencies, role ambiguity, and system and department variability within the
organization leads to interpersonal conflict (Del Pino-Jones et al., 2019; Kim et al., 2016; Saridi
et al., 2019; Stadick, 2020; Timmermans et al., 2017). While there are several sources of
interpersonal conflict, the most common sources relevant to interprofessional conflict center
around hierarchy, communication, and the work environment (Saridi et al., 2019; Stadick, 2020).
Unresolved interpersonal conflict is counterproductive and results in decision-making
problems, ineffective communication, lack of commitment to the team, and reduced trust
(Edmondson, 2004). Additionally, unresolved conflict reduces problem-solving and can become
destructive (Almost et al., 2016). Destructive conflict can damage relationships and demoralize
team members in ways that make the group’s mission less likely to be achieved and is an
inefficient use of resources. Furthermore, unresolved conflict, particularly destructive,

jeopardizes patient care (Almost et al., 2016; Kim et al., 2017; McKibben, 2017). On the other
hand, synergy and mutual respect are achieved when interpersonal conflict is effectively
managed. Patients also benefit from enhanced care delivery when interprofessional team
members effectively manage conflict. However, there is a humanistic component to teamwork,
and as a result, issues related to hierarchy, communication, and behaviors warrant further
exploration and discussion.
Hierarchy. Hierarchy is defined as the vertical difference between members in the
possession of socially valued resources and is a fundamental concept in the study of groups and
teams (Greer et al., 2018). Grailey et al. (2021) stated that a flat hierarchy promotes
psychological safety. In the inpatient setting, hierarchy is often inherent to medical and clinical
decision-making, and the traditional healthcare culture has fostered a hierarchical power
differential (Cullati et al., 2019). Likewise, the workflow in the acute and critical care
environment and the extremely high stakes of patient care can create a power differential (Cullati
et al., 2019; Ervin et al., 2018; Lee et al., 2015). Power differentials often lead to threats against
other professional’s identities, resulting in decreased trust, respect, teamwork, and collaboration
(Kim et al., 2017; Mitchell et al., 2019). According to Bajwa et al. (2020), most conflicts
involving healthcare professionals involve issues of hierarchy, either as a source of conflict or
consequence, or it impacts how one responds to the conflict. This is often evident in power
dynamics between physicians and other interprofessional healthcare team members. Physicians
often consider themselves as being ultimately responsible for other providers within the
healthcare team. However, when working as part of an interprofessional team, each person is
accountable to the group and the patient for their professional behavior (Almost et al., 2016;
Ervin et al., 2018). This potential power differential can lead to conflict. Additionally, historical

factors and past interactions contribute to conflict development and often set the stage for future
conflict and ineffective conflict management.
As the healthcare landscape continues to change, the effective use of teams is
increasingly critical; the focus shifts from provider roles within the traditional hierarchy to
expertise asymmetry (Burtscher et al., 2020). Expertise asymmetry differs from hierarchy as it
does not focus on status or power. Instead, expertise asymmetry captures team members'
qualitative differences in knowledge and skills. Higher levels of asymmetry indicate that
members perceive their task-related expertise to be qualitatively different but not necessarily
higher or lower than their teammates (Burtscher et al., 2020). Expertise asymmetry also allows
for collaboration and shared decision-making. When teams are open-minded, value professional
differences, and effectively communicate and debate diverse and divergent views, the focus
becomes less on “me” and more on “we.” There is less focus on hierarchy, reduced tensions, and
improved team identity (Mitchell et al., 2019; Mitchell & Boyle, 2015).
Communication. Effective interprofessional collaboration requires strong
communication skills and is essential to teamwork, particularly in high-stakes settings such as
the ICU. Given the interdependence, urgency, and unpredictability of tasks in the ICU, the free
and open transfer of information is considered vitally important (Ervin et al., 2018). With
effective and supportive communication, individuals can acknowledge and address
misunderstandings before conflict escalates; it helps mitigate stress, enhance collaboration, and
decrease stress and burnout (Avgar & Neuman, 2015; Glymph et al., 2015; Moreland & Apker,
2016; Vogus & Iacobucci, 2016). Interpersonal conflict can be mitigated by stimulating open
communication and fostering innovative solutions that improve team performance.

On the other hand, ineffective communication prevents expression and clarity, facilitates
conflict escalation, and perpetuates detrimental outcomes, including role ambiguity, team
dysfunction, and decreased job performance, to name a few (Andregard & Jangland, 2015;
Avgar & Neuman, 2015; Kim et al., 2017; Moreland & Apker, 2016). Ineffective communication
includes condescending tones, pessimism, lack of formal or appropriate communication changes,
and the lack or unwillingness to effectively communicate (Foronda et al., 2016). Patient safety
issues also arise due to ineffective communication (Avgar & Neuman, 2015; Glymph et al.,
2015; Moreland & Apker, 2016; Rowland, 2017; Sexton & Orchard, 2016). It is widely accepted
that when communication within the healthcare team breaks down, patients are at a much greater
risk of adverse outcomes (Henrich et al., 2016).
Conflict in the workplace can result in poor collaborative attitudes and communication
among interprofessional healthcare team members. Therefore, all team members must
communicate effectively to avoid unilateral decision-making and failure to account for the
different team member’s perspectives (Cullati et al., 2019). Similarly, a study by Ewashen et al.
(2013) demonstrated that nurses and physicians had difficulty negotiating or managing
interprofessional conflict during intensive ethical situations. In that vein, there is an implicit
connection between communication, psychological safety, ethics, and conflict. A concept
analysis conducted by Ito et al. (2021) also found psychological safety and communication to be
closely connected. In their research, Ito et al. (2021) found that psychological safety in
healthcare work environments influences proactive behaviors such as asking questions, reporting
errors, and promoting open communication.

Conflict Management in the Workplace
While conflict is a ubiquitous term, it remains pervasive, and the lack of widely accepted
definitions and theories makes studying conflict management in the ICU or acute care setting
challenging. The consensus held by conflict researchers is that conflict can be better managed
than it often is (Bercovitch et al., 2009; Hocker & Wilmot, 2018; McCorkle & Reese, 2018). The
successful management of conflict in the workplace hinges on several factors, but ultimately,
conflict management, particularly in organizations, involves living with the conflict using
effective macro-level strategies. These strategies help curtain the dysfunction of conflict and
enhance constructive function to improve organizational learning and effectiveness (Rahim,
2002). It is important to note that there is a difference between conflict resolution and conflict
management (Rahim, 2002; Robbins, 1978). Conflict resolution is defined as eliminating or
terminating conflict through a process such as mediation, negotiation, or bargaining (Rahim,
2002).
Historical Overview of Conflict Management Research. While there remains a lack of
universally accepted definitions and theories, conflict management history can be traced to the
1930s. Advances in psychology and sociology, including the works by Holt and Brown (1931),
Dollard et al. (1939), Miller and Dollard (1941), and Follett (1942), set the foundation for
contemporary conflict management. Mary Parker Follett was an American social worker known
as the "mother of modern management." A revolutionary leader, Follett is one of the pioneers in
organizational theory and behavior (Gehani & Gehani, 2007).
Follet introduced the concept of constructive conflict, in which conflict should be
considered inevitable and essential for personal and organizational growth. Furthermore, Follett
noted that individuals respond to conflict in three manners: dominating, compromising, or

integrating (Gehani & Gehani, 2007). Lewin (1935) examined the fundamental management of
conflict via a force field theory in which interpersonal conflict is managed in one of three ways:
(1) approach-approach (positive), (2) avoidance-avoidance (negative), and (3) approach-
avoidance (positive/negative). In conflict, individuals must choose to resolve conflict to get rid
of tension.
Conflict Management Styles. Blake and Mouton (1964) introduced the Managerial
Grid to help leaders effectively lead and manage (using one of five different management styles)
by balancing the people's concerns against the organization's concerns. They contend that the
leader is most effective when they can effectively balance these two needs. More importantly,
they argued that leaders could be most effective when they know their management style. Blake
and Mouton (1964) acknowledge that outside factors impact their style, including personal and
organizational values, beliefs, and personality. Despite criticism, Blake and Mouton's (1964)
work is still considered by many to be one of the most respected and foundational works in
conflict management and organizational leadership.
Thomas and Kilmann (1974) extended Blake and Mouton's (1964) work by postulating
that individuals typically use one of five modalities to manage conflict: (a) avoiding, (b)
competing, (c) accommodating, (d) compromising, and (e) collaborating. Organizations and
leaders recognize that their leaders and staff must manage and mitigate conflict productively.
Increased attention to the role of effective communication, psychological safety, and successful
conflict management can help create an environment in which conflict can be significantly
managed (Bercovitch et al., 2009; Hocker & Wilmot, 2018; McCorkle & Reese, 2018).
Individuals respond to conflict in either a constructive or destructive manner and either
engage in defensive or supportive communication processes depending on environmental and

contextual factors such as personal development, experience, situational context, and the specific
relationships involved in the conflict (Gibb, 1961; Hocker & Wilmot, 2018; McCorkle & Reese,
2018; Moeller & Kwantes, 2015). The Dual Concerns Model by Blake and Mouton (1964), later
influenced and revised by the works of Thomas and Kilmann (1974) and Rahim (1983), is one
model used to explain how individuals respond to conflict. Using assertiveness (concern for self)
and empathy (concern for others; see Figure 1), the DCM purports that individuals will either
avoid or engage in conflict (Blake & Mouton, 1964; Fleming & Shaw, 2019; Hocker & Wilmot,
2018; McCorkle & Reese, 2018; Rahim, 1983; Thomas & Kilmann, 1974). Rahim (1983) further
evolved the theory of conflict management by qualifying the styles as (a) avoiding, (b)
integrating, (c) obliging, (d) compromising, (e) dominating, and (f) avoiding, While the exact
terms may vary depending on the researcher, the taxonomy of avoiding, competing,
accommodating, compromising, and collaborating remain they key terms used today.
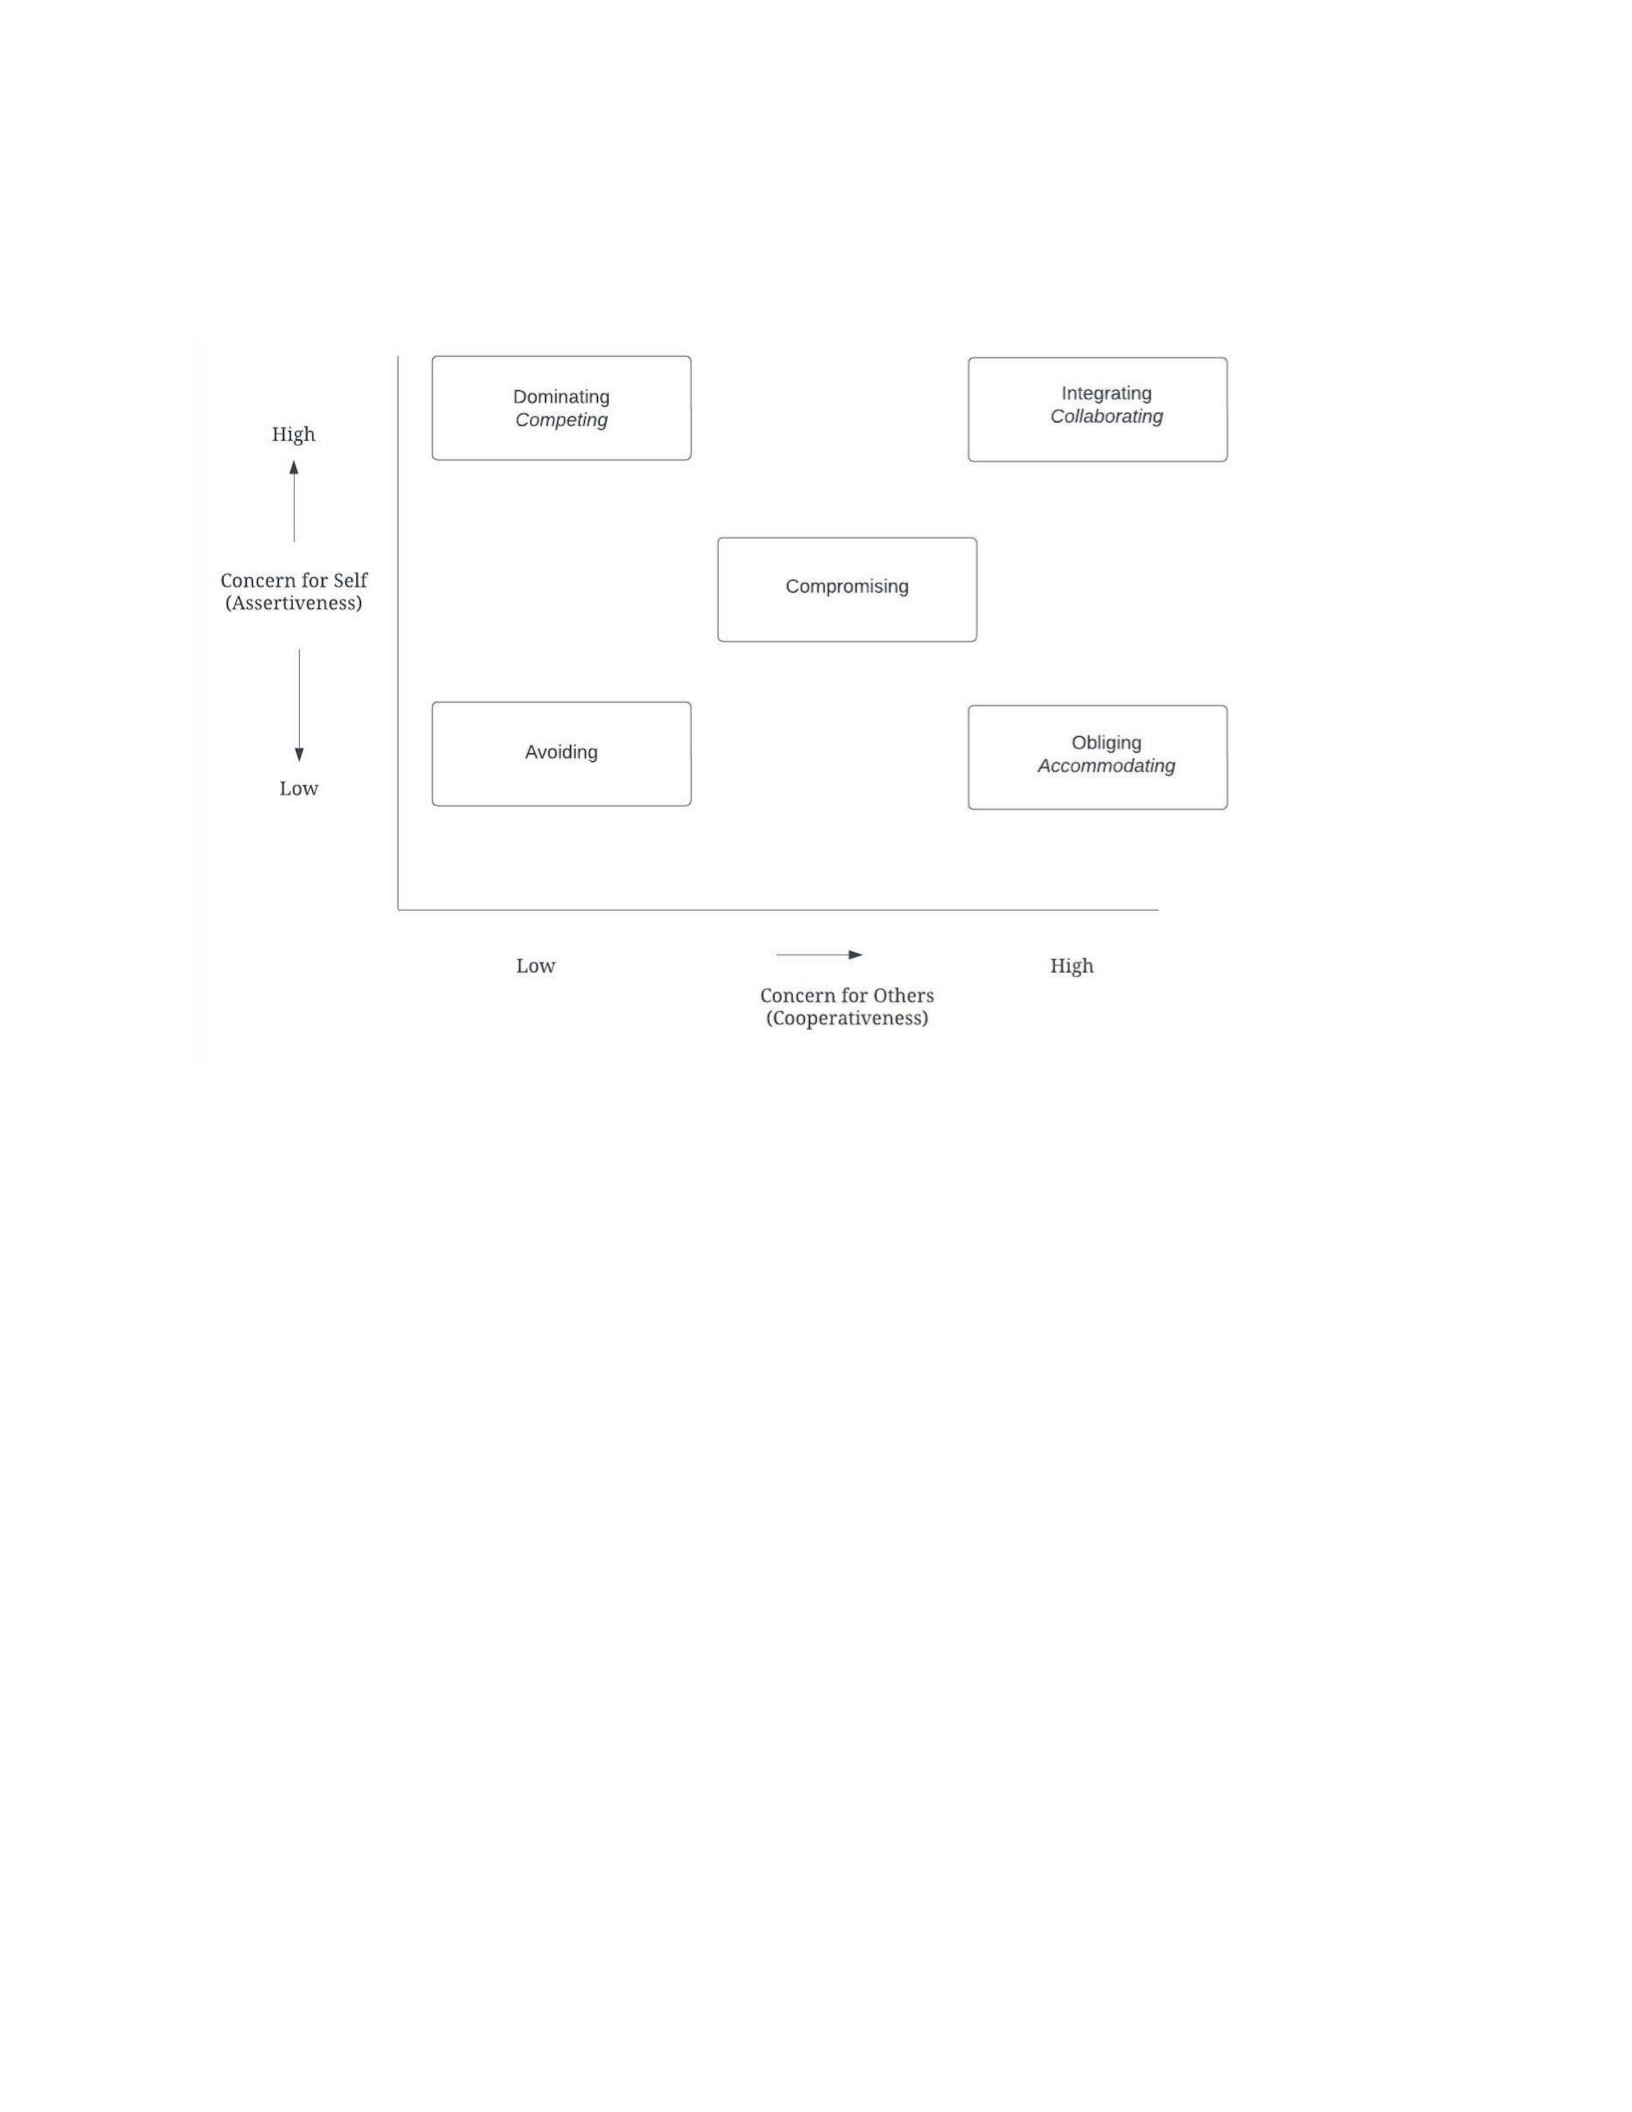
Figure 1
Conflict Management Model
Note. Conflict Management Model. Adapted from "Thomas-Kilmann Conflict Mode Instrument
by John E. Jones, 1976, Group and Organization Studies, 1(2), 250. Copyright 1976 by
University Associates.
Avoiding. Individuals with an avoiding conflict management style show little or no
concern for themselves and others, ultimately disregarding responsibility and not addressing the
issue. However, by avoiding the situation, the individual potentially delays the inevitable,
escalating the problem (Fleming & Shaw, 2019; Hocker & Wilmot, 2018; Rahim, 1983; Thomas
& Kilmann, 1974). This style is sometimes beneficial, depending on the circumstances and the
issue's importance. Unfortunately, using the avoiding style results in a lose-lose outcome.
Competing. Individuals with a competing sometimes called forcing or dominating,
conflict management style show high concern for themselves and little concern for others. This

style creates an imbalance and power differential, resulting in a win-lose outcome (Fleming &
Shaw, 2019; Hocker & Wilmot, 2018; Rahim, 1983; Thomas & Kilmann, 1974).
Accommodating. Individuals with an accommodating conflict management style, also
called obliging or yielding, show little concern for themselves and a significant concern for
others. This style creates an inverse power imbalance and differential, resulting in a lose-win
outcome (Fleming & Shaw, 2019; Hocker & Wilmot, 2018; Rahim, 1983; Thomas & Kilmann,
1974).
Compromising. Individuals with a compromising conflict management style take a
middle-of-the-road approach, requiring both parties to negate demands and desires to achieve an
outcome. With this style, issues may arise if individuals compromise too soon in the conflict
management process. Likewise, this style is often inappropriate for complex issues as it requires
both parties to concede potentially essential aspects of demands or desires (Fleming & Shaw,
2019; Hocker & Wilmot, 2018; Rahim, 1983; Thomas & Kilmann, 1974).
Collaborating. Individuals with a collaborating conflict management style, also referred
to as mutual benefit, integrating, or problem solving, engage in mutuality and show a significant
concern for themselves and others. This style allows for collaboration and facilitates trust and
relationship building, resulting in a win-win outcome. This synergistic approach has been
mathematically expressed by the formula A + B = Z instead of A + B = C (Fleming & Shaw,
2019; Hocker & Wilmot, 2018; Rahim, 1983; Thomas & Kilmann, 1974). The primary limitation
of collaboration as a conflict management style is that it is time-intensive, and manipulation by
one or both parties is possible (Fleming & Shaw, 2019; Hocker & Wilmot, 2018).

Empirical Research on Conflict Management Styles in Healthcare
Conflict management styles in healthcare are a relatively new field of research. Studies
specific to nurse practitioners in ICU settings were not identified; however, four studies were
located that are specific to healthcare settings. The four studies measured conflict management
styles in healthcare settings using the Thomas-Kilmann Conflict Mode Instrument (TKI; Jones,
1976). These studies differed significantly in setting, sample size, and type of healthcare provider
studied. Further, only one study was conducted in an ICU setting (White et al., 2020). Therefore,
it is difficult to determine if nurse practitioners who work in acute care and critical care settings
have an overall preferred conflict management style.
One of the earliest studies on conflict management styles in a healthcare setting was
conducted by Ogunyemi et al. (2010). Ogunyemi et al. (2010) used the TKI to survey 19
physician residents in an OB/GYN setting in Los Angeles, California. Of the 19 participants, six
also had administrative and teaching responsibilities and were classified as contributors. The
authors aimed to determine if there was a relationship between residents’ behavior and conflict
management style. The authors found that “accommodating” was the most commonly reported
conflict management style, and “collaborating” was the least reported conflict management style.
When comparing the scores for contributors to all other participants, contributors reported higher
“competing” scores. The authors also noted a significant correlation between high “compliance”
behavior scores and the tendency to compete or collaborate when managing conflict.
Conversely, residents with lower compliance behavior scores were more likely to
accommodate or avoid when managing conflict. The authors concluded that unique stressors
may modify an individual’s conflict style (Ogunyemi et al., 2010). A significant limitation of this

study is the small sample size; it was unclear if the authors conducted a power analysis and
achieved the statistical power needed to produce statistically significant findings.
The only known study of ICU providers was conducted by White et al. (2020), who
assessed a conflict management education intervention with a pre- and posttest of 49 ICU
providers at a medical center in Texas. Providers included 10 physicians, 18 registered nurses,
nine respiratory therapists, and 12 unspecified providers. Overall, the participants had clinical
experience ranging from less than 1 year to 30 years or more. The authors found that 32% of
participants avoided conflict (avoiding conflict style), while 30% compromised when faced with
conflict (compromising conflict style), 9% collaborated (collaborating conflict style), and 5%
competed (competing conflict style). Given this data, the authors found that avoiding and
compromising were the preferred conflict management styles among providers in ICU settings,
and there were negative team outcomes associated with compromising and avoiding. Ultimately,
the authors reported that the intervention (a 1-hour training class on conflict management
concepts) successfully increased knowledge of conflict management (White et al., 2020).
Pitsillidou et al. (2018) assessed the conflict management styles of health professionals in
Cyprus hospitals using the Conflict Health Professional questionnaire (Kontogianni et al., 2011;
Pavlakis et al., 2011). Respondents included 300 health professionals from six different hospitals
in Cyprus. A majority of participants were female (74.3%), had more than 10 years’ experience
(43.5%), did not have an administrative position (80.9%), and were prepared at the diploma or
bachelor’s degree level (68.2%). Results indicated that 73.2% of participants used avoidance as
their conflict management style, 54.2% used negotiation for mutual benefit, and 40.5% cited
compromise as their dominant style for managing conflict. The two styles reported least by
respondents were assertiveness (13.7%) and arbitration (21.4%). The authors noted that

providers with more than ten years of experience were significantly more likely to be assertive in
managing conflict (p < .01). In contrast, providers with six to 10 years of work experience tended
to negotiate to resolve conflict. When examining specific provider types, nurses with more than
six years of experience had a significantly lower tendency to compromise and appeared more
assertive in resolving conflict (p < .001). However, a study by Borou et al. (2013) found that
nurses with at least ten years of experience were more likely to resolve conflict through
compromise. Although, it is possible that the difference in years of experience could account for
this difference.
Vasilopoulos et al. (2018) examined the conflict management styles of 22 first-year
postgraduate anesthesiology residents at an academic medical center in Florida. Two different
instruments were used, the TKI and the Dutch Test for Conflict Handling (DUTCH). The TKI
was used as a self-assessment to measure the five conflict styles (i.e., collaborating, competing,
accommodating, avoiding, and compromising). The DUTCH was used as a self-assessment and
counterpart assessment after residents participated in a conflict scenario to measure five conflict
styles (i.e., yielding, compromising, forcing, problem-solving, and avoiding). Residents
predominantly take a more cooperative and problem-solving approach to handling conflict.
However, the authors noted that while individuals have a dominant conflict management style,
they will adapt to handling conflict based on the context. Therefore, it is essential for individuals
to self-assess their conflict style, so they are aware of their default response and are more capable
of adapting in specific contexts. There were no significant differences between self and
counterpart ratings on the DUTCH. Overall, the correlations between the TKI and DUTCH
scores were not statistically significant (p >.05). However, the authors indicated that the study
was underpowered and might not have detected moderate correlations.

Context is vital in the consideration of an individual's conflict management style.
Researchers of conflict management have observed that individuals adapt their conflict
management style based on the context of the conflict (Callanan et al., 2006). The importance of
context is evident in analyzing the findings of the four studies identified. Given the lack of
literature specific to critical care and acute care settings with nurse practitioners, there is a need
for additional research in this area. These settings are unique in that they are highly temporal and
are characterized by high stakes, increased opportunity for errors, and the need for collaboration
among multiple providers. Thus, it is essential to understand how conflict management styles
might differ in these contexts.
Psychological Safety
A psychologically safe environment allows individuals to challenge the status quo,
identifying problems or opportunities for improvement without fear of retribution (Burris et al.,
2009; Nembhard & Edmondson, 2006). Psychological safety also influences how individuals
manage conflict, indicating whether team members can be open, truthful, and honest with one
another without fear of retaliation (Edmondson, 1999, 2019). According to Schein and Bennis
(1965), who conducted the earliest known research on psychological safety, teams can overcome
defensiveness and learning anxiety when all members feel psychologically safe. Further, a
climate of psychological safety can mitigate the interpersonal risks inherent in teams, particularly
traditionally hierarchical teams, such as interprofessional health teams. Therefore, understanding
team members’ perceived psychological safety is essential when studying conflict management
within interprofessional healthcare teams.
As with conflict management styles, context is critical when studying psychological
safety. Edmondson et al.’s (2001) work highlighted the importance of context when they

examined the impact of clinical leadership and psychological safety during the implementation
of a new surgical procedure (i.e., less invasive cardiac surgery). The study found that surgeon
(leader) accessibility was significantly associated with differences in how the team functions and
members’ perceptions of psychological safety. Leaders who sought input from team members
were more likely to encourage psychological safety. Soliciting feedback suggests to others that
their opinion is respected. At the other end of the spectrum, leaders who discourage input or
discussion create an environment or contextual setting where team members are less likely to
express their opinions, often fearing potentially negative consequences. The extent to which a
surgeon (leader) encourages input and feedback from other members varied considerably across
the site in the study. Likewise, how team members behave is likely to respond to the contextual
environment as this replicates or mimics the behavior of leaders and illustrates the implication
that power in an organization is inevitable and input in communication is required for conflict
management success. This allowed other team members to perceive their environment as safe to
discuss mistakes and make observations.
Similarly, Grailey et al.’s (2021) research supports the importance of context in
psychological safety. The authors noted that individual, team, and organizational contextual
factors promote or impede psychological safety. Location, personality, previous experience,
culture, and the individual’s confidence level impact psychological safety. From an
organizational perspective, factors such as hierarchy, alternative routes to communicate
concerns, culture, and organizational support play an important role in psychological safety.
While individual and organizational factors are both important, it is equally important to note the
contextual aspects of psychological safety at the team level, especially since one of the
objectives of the proposed study is to examine the relationship between psychological safety and

conflict management at the team level. Team-level contextual factors that either promote or
impede psychological safety clearly define team member roles, leader involvement, and the
personality of team members (Grailey et al., 2021).
Edmondson et al.’s (2001) and Grailey et al.’s (2021) findings bring attention to clinical
culture and interpersonal context in the clinical setting. For example, when nurses have issues,
feel intimidated, or cannot successfully communicate with attending physicians, they will often
seek input and share with the NP or PA instead of communicating with the attending physician.
Similarly, Edmondson et al. (2001) noted that culture and context play a key role, especially in
healthcare, where the culture is traditionally hierarchical. Individuals who either perceive
themselves or are considered by others to be on the lower end of the hierarchy (i.e., nurses and
support staff) are often unwilling to risk censure by individuals on the higher end of the
hierarchy scale (i.e., physicians). Edmondson et al.’s (2001) findings support this claim.
In Edmondson et al.'s (2001) study, the authors found that individuals of lower status
were often unwilling to risk censuring by experienced medical staff who might view their input
or comment as useless or disruptive. The authors also reported that psychological safety seemed
particularly important for enabling the behavioral changes needed for nurses and support staff to
voice their concerns. For example, NPs may be perceived as having a lower status than
physicians, and without psychological safety, NPs may not express their concerns. Furthermore,
a later study by Edmondson (2012) and subsequent findings support that when leaders (clinical
and nonclinical) empower a team, the learning process is significantly impacted such that the
team's ability to learn a new skill or process is improved. Understanding the role of context in
every scenario is essential to enhancing psychological safety within the clinical environment.
Knowing what factors can influence the context and ensuring the clinical team possesses enough

psychological safety to take a risk minimizes the likelihood of clinical error and fosters a culture
of innovation (Edmondson, 1999, 2012; Ito et al., 2021).
Contemporary Perspectives Regarding Psychological Safety. Psychological safety
research remained dormant until 1990, when Kahn (1990) explored how psychological safety
enables personal engagement at work. Participants included summer camp counselors and
members of an architecture firm. The general link between personal attention and psychological
safety was explored. The researchers found that personal engagement was associated with higher
levels of psychological safety (M = 7.7, SD = 1.21) compared to personal disengagement (M =
3.77, SD = 1.6; r = .83). These findings suggest that individuals who are personally engaged in
their work experience a higher degree of psychological safety than those who are disengaged.
Furthermore, the authors noted four factors directly influencing psychological safety: (a)
interpersonal relationships, (b) group and intergroup dynamics, (c) management style and
process, and (d) organizational norms.
Amy Edmondson’s work on psychological safety also began in the 1990s when she
became interested in team learning behavior. Edmondson (1999) believed that team outcomes
and, ultimately, team performance are shaped by team structure, team leader support and
coaching, and shared beliefs. Through studying team learning behavior, which Edmondson
(1999) defined as the “activities carried out by team members through which a team obtains and
processes data that allow it to adapt and improve” (p. 351), it was discovered that individual
beliefs about the interpersonal context vary between team members in the same organization,
which affects team performance. Edmondson’s (1999) model of team learning helps understand
the role of psychological safety in studying team performance and, ultimately, how a team
successfully manages conflict.

Psychological safety is associated with strong interpersonal relationships and requires a
culture that values collaboration, trust, and innovation, ultimately impacting patient safety and
outcomes. Despite the extensive and dynamic nature of research regarding psychological safety,
a culture of fear and low psychological safety still exists within many healthcare organizations
(Edmondson & Lei, 2014; Swendiman et al., 2019; Unal & Seren, 2016). However, the ongoing
COVID-19 pandemic has highlighted the importance of psychological safety within healthcare
teams. Cultivating psychological safety requires healthcare teams to collectively redesign
processes and services to cope with new challenges, learn from mistakes, and implement changes
accordingly (Stoller, 2020). Like context, trust is also a key indicator of a team’s psychological
safety and the overall setting.
Psychological Safety and Trust. Like psychological safety, trust captures elements of
vulnerability and risk one perceives in the workplace (Edmondson, 2004). Edmondson (2004)
differentiated the two constructs by highlighting the focus of each construct. Trust captures one’s
willingness to be vulnerable to others, thus demarcating one’s willingness to give the other
person the benefit of the doubt. Psychological safety, on the other hand, captures the extent to
which one believes that others will provide them with the benefit of the doubt when taking risks
(Edmondson, 2004).
Psychological safety and trust share key features of psychological safety, but these terms
are not synonymous. Trust is a necessary prerequisite for psychological safety; it is the
expectation that others’ future actions will be favorable to one’s interests. Conversely,
psychological safety is a climate where people are comfortable expressing themselves. Although
both constructs involve a willingness to be vulnerable to another’s action, they are conceptually

and theoretically distinct. In the simplest form, psychological safety centers around group
behaviors and norms, while trust is transactional and reduces the need to monitor behavior.
Edmondson (2004) noted that psychological safety has three elements that distinguish it
from trust - the object of focus (self-versus other), time frame (narrow temporal bounds), and
level of analysis (group level versus individual). While the constructs of psychological safety and
trust have unique nuances, there are also several key similarities. Both constructs involve
perceptions of risk for vulnerabilities and making choices to minimize negative consequences,
and both have potentially positive impacts on groups and organizations.
Psychological Safety at Different Levels: Individual, Team, and Organizational.
Psychological safety has been studied as an individual, organizational, and group-level
phenomenon. Schein and Bennis (1965) and Kahn (1990) examined psychological safety from
an individual’s perspective, while Edmondson’s work primarily examined psychological safety
from the team’s perspective. Edmondson (1999) argued that psychological safety is best studied
from a group-level phenomenon. It is, therefore, essential to acknowledge how psychological
safety appears from different perspectives. Ito et al.’s (2021) research supports Edmondson’s
(1999) assertion that while psychological safety has individual and organizational components,
the construct is best studied at the team or group level.
From an individual perspective, psychological safety has been examined from an input-
process-output model focusing on outcomes such as professional engagement, organizational
commitment, and quality improvement. The interpersonal experience of psychological safety is
fundamental in facilitating personal behaviors essential to effectively manage conflict and
engage in growth and development, regardless of the level of engagement (i.e., individual,
organizational, or group). More specifically, research studies regarding psychological safety and

the individual have focused on employee behaviors (Deteret & Burris, 2007). Regardless of
whether one ascribes to the origin of psychological safety from an individual or group-level
perspective, it is clear that both perspectives view psychological safety as creating an
environment that facilitates “the contribution of ideas and actions to a shared enterprise”
(Edmondson & Lei, 204, p. 24).
More importantly, positive interpersonal relationships drive psychological safety
(Carmeli & Gittell, 2009; May et al., 2004). Positive relationships, influential role models, and
teamwork climates within healthcare teams encourage healthcare professionals to speak up
(O’Donovan & McAuliffe, 2020). Team members' relationship with the team leader has been
found to influence their sense of psychological safety. For example, when leaders engage in
supportive behavior, such as inclusiveness and openness, they foster psychological safety for
other team members (Appelbaum et al., 2016; Aranzamendez et al., 2015; Edmondson, 1999,
2019; Edmondson & Lei, 2014; Edmondson & Smith, 2006; Grailey et al., 2021; Ito et al.,
2021).
Regarding organizational research, Edmondson and Lei (2014) noted that organizational-
level research has traditionally focused on psychological safety and human resource practice
(i.e., culture, climate, and relationships). Edmondson and Lei (2014) found that psychological
safety is either a mediator or moderator between organizational antecedents and outcomes,
particularly in performance and learning. At the organizational level, only two known studies
have evaluated psychological safety (Baer & Frese, 2003; Carmeli, 2007). These two studies
evaluated employee perceptions of psychological safety within their organization based on
Edmondson’s (1999) team-level measure; however, they replaced the term “team” with
“organization” (Newman et al., 2017). The researchers then aggregated the organizational-level

data based on high intraclass correlation coefficients between organizational members. However,
caution must be noted as there should be relatively high levels of agreement between members of
an organization for an organizational climate of psychological safety to exist. There is a concern
that high levels of agreement between organizational members are unlikely, especially in larger
firms where employees are unlikely to have shared experiences of leadership and team norms. In
addition to Edmondson (1999), Newman et al. (2017) argued that psychological safety is likely
more potent and meaningful at the team rather than the organizational level.
Psychological safety continues to gain recognition as a vital construct in healthcare. To
garner a deeper understanding of the construct, Grailey et al. (2021) completed an evidence
synthesis examining the impact of psychological safety at the individual, team, and
organizational levels. Through the literature review, Grailey et al. (2021) noted there are barriers
and facilitators to psychological safety depending on the level of the phenomenon studied.
Overall, the authors identified nine attributes ranging from infrastructure to workload. Similar to
other studies, there is a certain degree of overlap between the different levels (e.g., culture and
teamwork). Similar to other reviews (Frazier et al., 2017; Newman et al., 2017), attributes such
as safety, culture, and self-efficacy are a recurring theme.
Key overall findings from Grailey et al.’s (2021) study suggest that individuals with
higher degrees of psychological safety are critical to effective and safe patient care and
organizational learning as they can communicate, adapt, and support themselves and each other.
Reassuringly, psychological safety was demonstrated in the studies reviewed to varying degrees.
As to be expected based on the studies, there are areas in which psychological safety is either
low or absent. Although none of the studies identified in the review demonstrated a statistically
significant correlation between low levels of psychological safety and adverse patient outcomes,

participants expressed strong feelings that low levels of psychological safety led to poor
outcomes.
Measurements of Psychological Safety. One of the challenges of evaluating
psychological safety is that most research examining psychological safety has been conducted at
the team level using Edmondson’s (1999) seven-item psychological safety subscale. A
systematic review by Newman et al. (2017) and a meta-analysis by Frazier et al. (2017) found
that most studies examining individual perceptions of psychological safety used the same or
similar constructs as Edmondson. However, some researchers (i.e., De Clercq & Riuz, 2007)
created instruments to measure psychological safety.
According to Frazier et al. (2017), using measures that are not specifically Edmondson’s
raises concerns about the divergence and meaning of Edmondson’s psychological safety
measures. Additionally, examining measures that are not precisely Edmondson’s without first
establishing their merit is psychometrically risky as it is unclear if the measures have the same
degree of validity as Edmondson’s (1999) and can lead to erratic findings (DeVellis, 2003). On
the other hand, Edmondson’s (1999) seven-item psychological safety subscale was developed
based on rigorous scale construction protocols and has been subjected to extensive validation
tests demonstrating strong content, criterion, and construct validity. Furthermore, Edmondson’s
(1999) measure of psychological safety has consistently been found to be reliable across diverse
samples, as all of the studies reviewed using her seven-item measure reported very good internal
consistency reliability estimates (Frazier et al., 2017; Newman et al., 2017; O’Donovan &
McAuliffe, 2020).
Antecedents to Psychological Safety. Antecedents to psychological safety can be
arranged into four broad categories: (a) interpersonal relationships (relationship networks), (b)

group dynamics (team characteristics, work design), (c) leadership (supportive/positive
leadership behaviors), and (d) organizational norms (supportive organizational practice, learning
orientation, supportive work environment, and organization; Edmondson, 1999; Frazier et al.,
2017; Ito et al., 2021; Kahn, 1990; Newman et al., 2017). Other researchers have noted proactive
personality (Deteret & Burris, 2007; Edmondson & Mogelof, 2005) and emotional stability
(Kahn, 1990) as antecedents to psychological safety. Openness to experience was initially
thought to be a key antecedent; however, a meta-analysis conducted by Frazier et al. (2017)
found this not to be the case.
Frazier et al. (2017) conducted the most recent comprehensive meta-analysis on
psychological safety. Frazier et al. (2017) searched for articles that cited Edmondson’s (1999)
work on psychological safety in the business and psychological literature. Primary studies that
reported statistical information and empirically assessed psychological safety were included in
the study. Of the 457 potential studies, 117 were chosen to include in the meta-analysis. The
authors followed the procedures established by Hunter and Schmidt (2004). They tested eight
hypotheses on psychological safety and its relationship to specific antecedents and outcomes at
the individual and group levels. The authors found the following antecedents positively
associated with psychological safety: (a) proactive personality, (b) emotional stability, and (c)
learning orientation. Learning orientation was included in Edmondson’s (1999) work. The
authors found group-level outcomes positively associated with psychological safety: information
sharing, citizenship behaviors, creativity, learning behaviors, commitment, and satisfaction. Of
these, learning behaviors aligned with Edmondson’s (1999) work.
While numerous antecedents to psychological safety are reported in the literature, the
antecedents most relevant to this study include the setting, population, and context, specifically

learning orientation and supportive work environment (Edmondson, 1999; Frazier et al., 2017).
Learning orientation in the acute care and critical care setting is crucial for understanding how
healthcare providers interact and manage patient care while also learning to collaborate as a
team. Furthermore, acute care and critical care providers need a supportive work environment to
deliver patient care effectively. Aspects of a supportive work environment include supportive
and positive leadership and group behaviors. Therefore, the following sections will discuss and
analyze the literature related to these specific antecedents.
Learning Orientation. Psychological safety enables learning orientation and behaviors at
the individual and team levels. This includes learning new skills and seeking help or feedback
(Carmeli & Gittell, 2009; Dweck, 1986, 2016; Edmondson, 1999; Edmondson & Lei, 2014;
Hirak et al., 2012; Ito et al., 2021; Sherf & Morrison, 2020). Learning orientation is best
described as how a team or organization encourages proactive learning and competence
development among its members to achieve and demonstrate positive outcomes, such as
adaptation and creativity. While it is essential for learning orientation to be present, its mere
presence does not always lead to team learning (Wiese & Burke, 2019). However, when team
learning occurs, patient safety is enhanced, as members can adapt appropriate behaviors to the
given situation through speaking up and other behaviors (O’Donovan & McAuliffe, 2020).
Teams whose members can trust their group members, feel respected, and communicate openly
are more likely to learn together and ultimately perform better over time. On the other hand, a
lack of psychological safety inhibits team members from speaking up and causes them to opt for
avoidance behaviors, such as silence (Sherf & Morrison, 2020).
An essential aspect of learning orientation is speaking up and sharing ideas. When
interprofessional team members feel psychologically safe, they can question the status quo and

ask honest and challenging questions without fear of appearing ignorant, incompetent, or
disruptive (Edmondson, 2019). In addition, in psychologically safe environments, individuals
can speak up openly and authentically with attention placed on the situation or problem and not
the individual. A psychologically safe environment allows individuals to innovate and progress
as knowledge is freely shared and ideas are explored (Edmondson, 2019).
Despite the varying sizes of teams within organizations, all teams must communicate and
share experiences to be successful. Studies have found statistically significant variations in the
psychological safety of different teams within the same organization. Nevertheless, individuals
who work closely together tend to have similar perceptions of team dynamics due to the social-
psychological mechanism at play. Moreover, individuals subjected to the same contextual
influences tend to have similar perceptions and shared expectations (Edmondson, 1999).
Supportive Work Environment. A supportive work environment is characterized by
effective supportive or positive leadership and group behaviors. A group, including the leader
and group members, must support building and fostering trusting and respectful interpersonal
relationships. Likewise, organizations and leaders must be capable of providing contextual
support and allowing for the emergence of group dynamics (Edmondson & Lei, 2014; Senge,
2006). Supportive leadership behaviors also include openness and honest communication
(Ahmed, 2019; Deteret & Burris, 2007; Edmondson, 2019; Hirak et al., 2012; Liu et al., 2014;
Nemanich & Vera, 2009), behavior integrity (Leroy et al., 2012; Palanski & Vogelgesang, 2011),
shared leadership (Liu et al., 2014), inclusiveness (Bienefeld & Grote, 2014; Nembhard &
Edmondson, 2006), support (Edmondson, 1999; May et al., 2004), and trustworthiness (Madjar
& Ortiz-Walters, 2009).

Kahn (1990) and Edmondson (1999) identified positive relationships with leaders as
having a crucial influence on the perception of psychological safety. Leaders who are accessible,
invite and actively seek input from others, and model openness and fallibility are more likely to
generate a sense of psychological safety than are leaders who are less accessible, engaging, and
perhaps punitive (Edmondson, 1999; Edmondson & Lei, 2014). Edmondson et al.’s (2001) study
of surgeons, nurses, and operating room personnel revealed that leaders who ask for team
members’ input likely encourage psychological safety. Conversely, when leaders discourage
input or discussion, verbal or otherwise, team members are less likely to express their opinions,
fearing potentially negative consequences.
Regardless of one’s leadership style, the social exchanges between leaders and followers
have a crucial impact on the overall expectations of what is and is not appropriate or acceptable
behavior (Edmondson, 2004). Newman et al. (2017) acknowledged that the social exchange
process may increase psychological safety, as they believe it is likely that the effects will be
more substantial and more enduring when psychological safety is built through learning and
emulating these behaviors from the leader. Influential leaders can model appropriate behavior to
their followers, noting that taking risks and engaging in honest communication is safe and
appropriate (Edmondson, 1999; Hirak et al., 2012; Liu et al., 2014). Edmondson (2001) also
found that team members will likely mimic the leader's behavior. For instance, if the actions of
leaders indicate that some issues are not open for discussion, then other team members will
follow their example.
A supportive work environment and culture and a psychologically safe environment led
to improved performance. Both early research (Carmeli et al., 2009; Carmeli & Zisu, 2009;
Kahn, 1990; Tucker et al., 2007) and contemporary research (Chen et al., 2014; Grailey et al.,

2021; Singh et al., 2013) captured the importance of an overall supportive work environment and
have been positively linked to psychological safety. Teams that are supportive and offer
organizational support (Carmeli & Zisu, 2009), mentoring (Chen et al., 2014), and diversity
(Singh et al., 2013) foster an environment that is conducive to success.
Psychological Safety and Conflict. Psychological safety is a critical environmental
factor influencing the interprofessional team and managing conflict (Edmondson, 1999, 2019).
While positive, supportive, and trusting interpersonal relationships can foster psychological
safety, it is essential to note that psychological safety does not imply that a team is without
conflict or problems (Edmondson, 1999, 2003). In contrast, psychological safety is needed for
productive conflict, such as task conflict, to occur (Hoenderdos, 2013). Task conflict concerns
disagreements about differences in viewpoints, ideas, and opinions about the task being
performed and can result in learning and improved performance (Bradley et al., 2012;
Edmondson & Lei, 2014; Hoenderdos, 2013). Psychological safety potentially influences how
conflict is managed by individuals who can voice their concerns without fear of retribution in a
psychologically safe environment. Such an environment would likely result in using a
collaborative conflict management style. On the other hand, inappropriate or dysfunctional
communication, especially in low psychological safety levels, has been shown to lead to medical
mishaps and less effective ways of managing conflict (Edmondson, 1996).
The inherent attributes of the interprofessional team, particularly in the acute or critical
care setting, can lead to conflict in the absence of communication. Interprofessional team
members must collectively understand each other’s roles and responsibilities; however, an
interprofessional healthcare team's varied roles and responsibilities can make effective
communication challenging. A 2015 report on malpractice claims in the United States implicated

communication failure as a contributor to 30% of all malpractice claims and 37% of high-
severity injury claims (CRICO Strategies, 2015). Effective communication within the
interprofessional team is facilitated by psychological safety, encourages collaboration, and helps
create an environment of optimal outcomes.
Psychological Safety, Communication, and Conflict Management. The constructs of
psychological safety and conflict management converge in the healthcare setting, particularly in
the acute and critical care environments, and are united through the lens of communication.
There is a dearth of evidence on psychological safety, conflict management style, and success.
However, there is ample evidence of the importance of communication and its role in conflict
management and fostering psychologically safe environments. Although some researchers do not
use the term “psychological safety” directly, it can be inferred that environments that foster open
communication are perceived as psychologically safe. Therefore, the literature presented in this
section will focus on empirical research that addresses communication as a vehicle for successful
conflict management, given the level of perceived psychological safety among healthcare team
members.
Open communication is critical to successful conflict management. Speaking up, making
suggestions, and challenging the status quo can create an environment where conflict can emerge
(Edmondson, 1999, 2019; Shein, 1985). Conflict management is a learned behavior, and a
psychologically safe environment allows individuals to overcome their anxiety and fear of
failure, which is often necessary for learning (Edmondson, 1996, 1999; Shein, 1985).
Furthermore, when individuals feel safe in their environment, they are more likely to want to
remain in their current environment with their coworkers (Edmondson, 1999).

Prior research demonstrates the role of communication and its positive impact on job
performance. It is also known that individuals have been hesitant to communicate negative
information upward when they are in a perceived psychologically unsafe setting, whereas
individuals in a psychologically safe environment are more willing to acknowledge issues and
voice concerns (Edmondson, 1996, 1999). While research indicates that dysfunctional
communication and low psychological safety leads to poor outcomes, until recently, the
correlation between communication and psychological safety in healthcare settings was lacking
(Yanchus et al., 2014).
Yanchus et al. (2014) conducted a mixed-method study that examined how psychological
safety facilitates effective communication among healthcare providers in teams with high and
low levels of psychological safety. This study was conducted as a part of planning organizational
interventions. Several themes emerged, including communication safety, interpersonal aspects of
communication, the impact of communication on employees, interpersonal aspects of
communication, leader response, hierarchy or status, and patient communication in high and low
psychological safety.
In terms of communication safety, or the extent of feeling comfortable providing input in
the workplace, teams that are psychologically safe noted perceptions of communication safety
16% of the time compared to those in teams with low psychological safety (6%). Teams
identified as being low in psychological safety noted communication safety as a weakness (31%)
compared to those with high levels of perceived psychological safety. Similar to a prior study by
Edmondson (2003), Yanchus et al. (2014) found that employees in psychologically unsafe
environments feel discouraged from using optimal or best practices and note fear of retaliation as
a frequent reason for remaining silent.

Another interpersonal aspect of communication emerged in literature. Interpersonal
communication refers to the level of openness, honesty, and trust between individuals. Not
surprisingly, individuals in teams with high levels of psychological safety cited this as a strength
more frequently (5%) than those affiliated with teams with lower levels of psychological safety
(1%). More importantly, individuals in groups with lower levels of perceived psychological
safety cited the lack of interpersonal communication as a weakness (18%) versus those affiliated
with teams with higher levels of psychological safety. Similarly, the degree or amount of
communication was cited as a weakness in groups with lower levels of psychological safety
(11%) compared to groups with higher levels of psychological safety (1%; Yanchus et al., 2014).
The role of the team leader and status were also communication-related themes similar to
the known antecedents of psychological safety. How supervisors and managers responded to the
needs of the groups was a reported weakness in teams with lower levels of psychological safety
(29%) versus not being evident (0%) in psychologically safe groups. The study by Yanchus et al.
(2014) noted that individuals in psychologically unsafe environments often viewed their leader’s
response to be negative. In terms of communication and status, communication between
individuals with varying power dynamics was more frequently cited as a weakness in groups
with higher levels of psychological safety (13%) versus groups with lower levels of
psychological safety (4%). While this finding is counterintuitive, it is not surprising, as one key
feature of psychological safety is comfort in identifying and discussing issues that arise. In this
study, it is likely that individuals affiliated with groups of higher psychological safety were more
willing to discuss their concerns about status issues, particularly issues pertinent to patient care.
Likewise, individuals who identify with being in a psychologically safe environment reported a
greater sense of communication, particularly in the degree and frequency with their leaders. One

of the most important themes that emerged from the research by Yanchus et al. (2014) is the
degree of communication-related to patient care. Teams exhibiting lower psychological safety
reported patient communication as a weakness (16%) compared to only 2% in high
psychological teams.
Psychological safety can be classified as either high, moderate, or low. An evidence
synthesis conducted by Grailey et al. (2021), which included 62 papers from 19 countries, found
that many methods were used without a clear or consistent methodology. Sixteen studies
demonstrated a predominantly low level of psychological safety. Fifteen studies could not
identify homogeneous findings (i.e., high and low levels of psychological safety), and six studies
reported high levels of psychological safety. Overall, the heterogeneity of the data around
individual healthcare providers and psychological safety across the 62 identified papers
prevented Grailey et al. (2021) from drawing an overall or generalizable conclusion about
psychological safety.
Conflict Management Success
While it is essential to understand the various dynamics of the multidimensional aspects
of interpersonal conflict experienced by nurse practitioners, including an individual’s conflict
management style and the role of perceived psychological safety when managing conflict, it is
also essential to define the concept of conflict management success and how it is evaluated. It is
also critical to consider how team conflict is defined. At a high level, team conflict is “a process
in which one’s perceived interests are being opposed or negatively affected by another” (Wall &
Callister, 1995, p. 517). The timing of when conflict occurs is also crucial when studying team
conflict.

According to Tuckman (1965), an early researcher of team conflict, team conflict
typically occurs when team members begin working together and express differences in values
and perspectives. On the other hand, Gersick (1988, 1989) found that teams develop conflict at
the midpoint of team development and collaboration. Regardless of the timing of the conflict,
team members can effectively manage task conflict when cohesion is established. Team cohesion
is the force and degree of interpersonal bond among a group's members. This interpersonal bond
allows members to participate willingly and remain engaged to accomplish team goals (Casey-
Campbell & Martens, 2009; Salas, Grossman, et al., 2015). When cohesion is established, a
stronger team identity emerges. Cohesion is closely aligned with psychological safety and the
collaborative conflict management style. All three constructs are rooted in positive psychology
and acknowledge the greater good while respecting concern for self and others. Despite this
general understanding of team cohesion and the management of task conflict, how individuals
and teams realize or become conscious of when conflict is successfully managed is not well
understood. The literature lacks a widely accepted definition of conflict management success
because conflict is a team process, and conflict management success is an emergent state of
awareness.
Researchers have attempted to define and evaluate conflict management success by
focusing on specific types of conflict (e.g., relationship, task, and process), team cohesion, and
satisfaction (Benitez et al., 2018; De Dreu & Weingart, 2003; de Wit et al., 2011; Greer et al.,
2018; Tekleab et al., 2009). Despite two critical meta-analyses (De Dreu & Weingart, 2003; de
Wit et al., 2011) and a study by Tekleab et al. (2009), no unifying agreement exists on defining
and evaluating conflict management success. For instance, De Dreu and Weingart’s (2003) meta-
analysis found that task conflict and relationship conflict are negatively associated with team

performance and team satisfaction, notably in situations characterized by high complexity (e.g.,
decision-making and team projects). While it is widely accepted that task conflict is positively
related to group outcomes via collective cohesion and decision-making, there is a concern that
conflict will spill over to relationship conflict when task conflict is not addressed (Edmondson &
Smith, 2006; Jehn, 1997; Jehn & Mannix, 2001). While task conflict positively influences
outcome variables, it does so when it does not cause relationship conflict. One constraint or
challenge of this argument is that relationship conflict will be negatively associated with team
effectiveness. However, this is not necessarily true, as conflict can be helpful when effectively
managed (Ervin et al., 2018; Field et al., 2014). The meta-analysis by de Wit et al. (2011) failed
to find a strong and negative association between task conflict and group performance. However,
in the same meta-analysis, task conflict and group performance were more positively related
among studies where the association between task and relationship conflict was weak. These
findings support the assertion that conflict management success is subjective and variable but is
related to group outcomes such as cohesion, team satisfaction, viability, and sustainability.
According to Tekleab et al. (2009), conflict management success is defined as a team’s
ability to work through conflict and maintain a cohesive state in which group members can
achieve the team’s goals or outcomes. The absence of a universal definition requires a critical
analysis of the literature. However, there is limited literature regarding conflict management
success due to the emergent subject nature of success. Of the various conflict management styles,
collaboration or integrating is most aligned with conflict management success. Individuals with a
collaborative conflict management style demonstrate concern for themselves and others. This
sense of concern leads to mutuality and facilitates trust and relationship building, promoting
cohesion, improved performance, sustainability, and satisfaction (Fleming & Shaw, 2019;

Hocker & Wilmot, 2018; Rahim, 1983; Thomas & Kilmann, 1974). When conflict is effectively
managed in healthcare settings, particularly in collaborative settings such as critical care units,
patient safety issues are appropriately addressed, and team members can build cohesion through
communication and collaboration (Edmondson, 2003; Edmondson et al., 2001; Edmondson &
Lei, 2014; Sexton & Orchard, 2016). Conflict management success is also theorized to be
impacted by the team's perceived degree of psychological safety.
Conflict Management Success and High Psychological Safety. High-quality
interpersonal relationships in the workplace have been found to play an integral role in
psychological safety (Carmeli et al., 2009; Edmondson, 2004) and have been directly implicated
in the increase in error detection rates (Edmondson, 1996) and conflict management success
(Tekleab et al., 2009). Furthermore, communication and relationships facilitate failure-based
learning (Carmeli, 2007). In failure-based learning, work groups improve their overall process
and procedures by acknowledging and reflecting on the underlying causes of previous errors.
Based on the findings from Grailey et al. (2021), what is known is that higher levels of
psychological safety leads to increased creative and technical team performance, knowledge
sharing, and quality improvement. Most importantly, the findings by Grailey et al. (2021)
support that higher levels of psychological safety are potentially associated with learning from
failure and lead to increased performance. While not directly discussed, it is fair to assume that
teams with higher levels of psychological safety will also be able to manage conflict effectively.
Teams with elevated levels of perceived psychological safety also tend to report mistakes
more than teams with lower levels of psychological safety. When adversity strikes, psychological
safety alleviates concerns, decreases the tendency to become defensive, and is inclined to discuss
issues and concerns (Kim et al., 2020). Psychological safety also allows for an accurate and

shared understanding of a situation by allowing members to socially construct reality through
sharing meaning and perspectives, so they cross over and converge at the team level (Stoverink
et al., 2020). When psychological safety is present and an error occurs, the team can shift from
blame to discovery, improvement, and growth. It is likely that teams using a responsive style of
conflict management or one that demonstrates high concern for self and others, such as
collaboration, can have difficult conversations without fear of retribution.
Effective team performance is contingent upon conflict, cooperation, coordination,
coaching, communication, and cognition between team members. Environments that respect
individuals, create value, and foster effective communication and security (i.e., high
psychological environment) allow for effective conflict management (Edmondson, 2019; Ervin
et al., 2018). In highly psychologically safe environments, individuals reported being able to
openly discuss ideas and concerns and describe their leaders as being active listeners who have
open-door policies. Individuals and teams with elevated levels of psychological safety are crucial
to effective and safe healthcare delivery and promote the organization's overall goals, including
learning. The individual and collective contributions that are demonstrative of high
psychological safety facilitate decreasing unnecessary risk and adapting from error, which leads
teams and organizations to find new pathways and processes that facilitate positive outcomes and
promote team cohesion (Grailey et al., 2021; Tekleab et al., 2009).
Conflict Management Success and Low Psychological Safety. Research demonstrates
that teams with low levels of psychological safety are more likely to engage in conflict, mainly
when working in a high-stress environment (i.e., the Emergency Department). Likewise,
individuals with low psychological safety tend to be a part of an environment that tolerates
yelling, profanity, and intolerance of divergent ideas. In teams with low psychological safety,

members feel less comfortable speaking up because of the negative social consequences of
potentially unfavorable or divergent views. Members experience negative emotions in response
to adversity with a narrowing of attention to focus on threats. These emotions will worsen in a
psychologically unsafe team where members hesitate to offer innovative or unique approaches.
The incidence of error reporting in high versus low psychologically safe environments is
also significant. The most frequent themes that emerge in connection with error reporting include
reporting patient care and patient safety issues, supervision, and culture, all connected to the
potential for conflict and conflict management success. Furthermore, in environments with low
levels of psychological safety, frequent themes include fear of retaliation, lack of organizational
responses, and lack of confidence in protection. Compared to teams with elevated levels of
psychological safety, teams with low levels of psychological safety are more likely to use less
responsive conflict management styles (e.g., avoidance and competing). They are less likely to
practice in a collaborative, cohesive environment. When conflict does emerge, individuals tend
to focus more on self-perseveration and less on maintaining team cohesion or ensuring optimal
organizational and patient outcomes.
Summary
Chapter 2 examines the salient and contemporary research of interpersonal conflict by
exploring (a) the dynamics of interprofessional teams, (b) the role of communication, (c)
psychological safety, and (d) historical and contemporary aspects of conflict and conflict
management, including psychological safety and conflict management success. Transitioning
from the literature review in Chapter 2, Chapter 3 will address the chosen methodology to study
the personal and environmental factors that impact the NP’s ability to successfully manage
interpersonal conflict that emerges from functioning as an interprofessional team member.

Chapter 3 will review the study's purpose, explicitly addressing the selected research
design and methodology (including defining the study sample, identifying selected
materials/instruments, and discussing data collection and analysis procedure). Ethical
considerations, assumptions, limitations, and delimitations will be included.

Chapter 3: Research Method
Advanced practice registered nurses, in particular nurse practitioners (NPs) are a vital
part of the interprofessional healthcare team; however, as more NPs are added to the team, the
likelihood of interpersonal conflict increases (Aberese-Ako et al., 2015; Avgar & Neuman, 2015;
Del Pino-Jones et al., 2019; Donald et al., 2015; Ervin et al., 2018; Glymph et al., 2015; Kim et
al., 2017; Rowland, 2017; Stadick, 2020). NPs enter the workforce with varying degrees of
communication and interpersonal problem-solving skills, which can impact their ability to
navigate and manage interpersonal conflict successfully and limits their ability to successfully
manage conflict (Cochran et al., 2018; Field et al., 2014; Moeller & Kwantes, 2015; Samuel et
al., 2015; Tekleab et al., 2009). The unresolved conflict has the potential to lead to unhealthy
work environments and jeopardize patient care and outcomes (Allen et al., 2019; Almost et al.,
2016; Avgar & Neuman, 2015; Glymph et al., 2015; Kleinpell et al., 2019). One of the critical
environmental factors that influences interprofessional teams and conflict is psychological
safety. While psychological safety has been examined in team settings, there is limited research
specifically examining the constructs of psychological safety, interpersonal conflict
management, and conflict management success. This chapter presents and justifies the research
methods and design. Elements addressed in this chapter include the study's design and method,
as well as the population, setting, and sample, including participant recruitment, data collection,
data management, and analytical strategies. A rationale for using the selected instruments and
support for their validity and reliability is also provided. The assumptions, limitations, and
delimitations are discussed. Finally, ethical considerations related to human-subject research are
presented.

Purpose of the Study and Research Questions
The purpose of this quantitative, cross-sectional, correlational study was to understand if
there were differences in perceived psychological safety associated with interpersonal conflict
management style and to theorize how perceived psychological safety predicts perceived conflict
management success among NPs working in an interprofessional acute or critical care team in
the United States. The following research questions guided this study:
RQ1. How do scores for perceived psychological safety differ based on interpersonal
conflict management style among NPs working in interprofessional acute care or critical care
teams in the United States?
H10. There are no statistically significant differences in perceived psychological safety
among NPs based on their conflict management style.
H1a. There are statistically significant differences in perceived psychological safety
among NPs based on their conflict management style, with NPs utilizing an integrating or
collaborating style of conflict management having higher levels of perceived psychological
safety than NPs who use other conflict management styles.
RQ2. How does psychological safety predict perceived conflict management success
among NPs working in interprofessional acute care or critical care teams in the United States?
H20. Psychological safety is not a statistically significant predictor of NPs' perceived
conflict management success.
H2a. Psychological safety is a statistically significant predictor of NPs' perceived conflict
management success, with higher levels of psychological safety predicting higher levels of
perceived conflict management success.

Research Design and Method
The study is a quantitative, cross-sectional, correlational survey (Appendix A). Research
questions drive the method of inquiry, and the questions and hypotheses in the study are
designed to allow the researcher to investigate the study variables (Fraenkel et al., 2019). A
quantitative study design is appropriate to answer the proposed research questions because the
researcher seeks to examine psychological safety, interpersonal conflict management style, and
successful conflict management using numerical data to answer the research questions and test
the hypotheses (Irwin, 2018). For the first research question, the different interpersonal conflict
management style categories, as noted by Rahim (1983), serve as the independent variable.
Edmondson's (1999) psychological safety construct is the dependent variable.
Regarding the second research question, the construct of psychological safety
(Edmondson, 1999) is regressed onto the construct of conflict management success (Tekleab et
al., 2009). The predictor variable is psychological safety, and the outcome variable is conflict
management success. Additionally, the study also evaluated the demographic covariates in both
questions.
A cross-sectional survey design was chosen to measure the proposed variables at a single
time. The selected survey method is appropriate as the study was nonexperimental and
economical, and the purpose was to explore the constructs of psychological safety, interpersonal
conflict management, and conflict management success at a single time and not longitudinally
(Polit & Beck, 2017). Furthermore, this study falls under the postpositivist paradigm, the primary
basis and anchor for quantitative methods (Polit & Beck, 2017). Whereas positivists recognize an
objective, discernable reality, postpositivists accept objective reality as impossible. Instead,
postpositivists view objectivity as a goal while remaining neutral (Polit & Beck, 2017).

Likewise, postpositivists view research as uncertain rather than focusing on absolute truth;
postpositivists focus on confidence or probabilistic evidence (Polit & Beck, 2017; Tanlaka et al.,
2019). Postpositivists seek to represent reality with their best effort and probability. The
interprofessional healthcare environment is dynamic in which conflict emerges and flexes; thus,
the context is uncertain and constantly changing. For these reasons, the postpositivist frame is
central to nursing and healthcare research. One of the key advantages of using the postpositivist
philosophy for this study is that it allows for the participant's unique perspective and addresses
the complexity of human phenomena (Polit & Beck, 2017; Tanlaka et al., 2019).
Qualitative and mixed-method approaches were considered but felt to be inappropriate
for several reasons. Often, qualitative research is used in healthcare, particularly nursing, to
address problems that cannot be reduced to variables or captured in numerical forms (Polit &
Beck, 2017; Rodgers, 2018). While personal interviews, observations, and content analysis may
provide depth to a small sample of responses, a qualitative approach will not be able to
determine if there are statistically significant differences in how psychological safety impacts
conflict management success among NPs working in interprofessional acute or critical care
teams.
Population
The target population for the proposed study included NPs working in interprofessional
acute care or critical care teams in the United States. According to the American Association of
Nurse Practitioners (n.d.), as of 2022, more than 355,000 NPs are licensed in the United States.
However, the exact configuration of NPs working in an acute or critical care environment is
unclear. Kleinpell et al. (2019) found 270,000 nurse practitioners employed in the United States.
In 2019, of the NPs employed in the United States, 28% identified working in the acute setting,

5.8 % in the Emergency or Urgent Care setting, and 12% in an Intensive Care or Critical Care
setting. The most appropriate classification of NPs for the study includes adult-gerontological
acute care nurse practitioner (AGACNP), acute care nurse practitioner, adult-gerontological
primary care nurse practitioner (AGPCNP), adult nurse practitioner (ANP), gerontologic nurse
practitioner (GNP), or family nurse practitioner (FNP). Nearly 123,660 NPs met the initial
qualification of practicing in the United States in an acute or critical care environment and are
the populational focus of the study.
Study Sample
Participants included NPs whose contact information was in an email listserv of 52,411
NPs currently practicing in the United States. The email listserv was obtained from the U.S.
Doctor Database, a commercially available third-party database that is updated monthly using
publicly available information obtained from the Centers for Medicare and Medicaid Services
(CMS) and the National Provider Identifier (NPI) registry search website. Due to low
participation rates, the study sample was expanded to include NPs from NP social media sites,
including Facebook and LinkedIn. To be eligible to participate in the study, participants must
meet the following criteria. Inclusion criteria:
● 18 years of age or older
● Licensed nurse practitioners (NPs) in the United States or territories
● At least (6) months of professional experience as an NP
● Currently working in an interprofessional acute or critical care team in an inpatient
setting
● Completed their professional NP training in the United States (Patino & Ferreira, 2018).
Exclusion criteria:

● Clinical Nurse Specialists, nonadvanced practice-prepared Registered Nurses, Certified
Nurse Anesthetist, Physician Assistants, Allopathic or Osteopathic Physicians
● Working exclusively in an academic or administrative role that does not involve direct
patient care
● Refusal to provide informed consent
A priori sample size was estimated using G*Power 3.1 (Faul et al., 2007). For all statistical tests,
the alpha cutoff was α = 0.05 and power β = 0.8. All tests are two-tailed unless otherwise
specified.
Sample Size
The sample size estimation for each research aim is as follows:
● RQ1. Are there statistically significant differences in scores for perceived psychological
safety based on the interpersonal conflict management style among NPs working in
interprofessional acute care or critical care teams in the United States? For the ANOVA
analysis (f = 0.25) with five independent groups (df = 4), the suggested minimum size
was n = 200 completed surveys.
● RQ2. How does psychological safety predict perceived conflict management success
among NPs working in interprofessional acute care or critical care teams in the United
States? Linear multiple regression with psychological safety and two potential covariates
predicting psychological safety (f2 = 0.15) requires a minimum sample size of n = 77.
● To compare differences in means between categorical demographic groups, a two-tailed
Student’s t-test (d = 0.5) requires a minimum group size of n = 64 for a total sample size
requirement of n = 128. The nonparametric alternative (Wilcoxon-Mann-Whitney) would
require slightly more, with a minimum of 67 per group and n = 134.

An ANOVA, with one independent variable (five groups) test, requires the highest
minimum sample size of n = 200. Thus, the sample size target was set at n = 400, which is
adequate for this study's primary objective while allowing for potential attrition, missing data,
and controlling for possible mediating/moderating factors or subgroup analysis.
Participant Selection
A list of 52,411 nurses was obtained from the database on October 7, 2022. The complete
list includes the individual's name, demographic, licensure/certification, organization affiliation,
and contact information (e.g., email addresses) of registered and advanced practice nurses in the
United States who either have an NPI number or are affiliated with CMS. The list was delivered
via email as a CSV file. Upon receipt of the list, I culled the ones that would potentially qualify
for inclusion, including NPs identifying as acute care, adult, critical care, or family nurse
practitioner, based on how the file was created (n = 30599; Appendix B). A separate database
containing two columns (i.e., type of NP and email address) was created. Upon IRB approval
(Appendix C), the recruitment process began by randomly choosing email addresses using a
random number generator in Excel (Appendix D). A separate secured spreadsheet with
randomized email addresses was created, and information was uploaded to a third-party secured
survey management program, Qualtrics. Qualtrics was used as the online survey platform to
administer the surveys (Appendix A). Due to a low response volume, recruitment was expanded
to include social media, including NP sites on Facebook and LinkedIn (Appendix F). The study
was open for ten weeks in the last quarter of 2022.
Materials/Instruments
Data collection consisted of a multi-item questionnaire containing demographic questions
and the use of three preexisting instruments: Rahim’s (1983) Organizational Conflict Inventory-

II (ROCI-II), Edmondson’s (1999) Team Learning and Psychological Survey, Psychological
Safety subscale (PSS), and Tekleab et al.’s (2009) Conflict Management Success subscale (CMS;
Appendix A). Permission to use the three instruments and the conflict management model figure
(Figure 1) was obtained from the authors and publishers (Appendix G). The selection of the
instruments to be used in the study is based on their validity and reliability in measuring the
constructs of interpersonal conflict management style, conflict management success, and
psychological safety. In addition to the survey, a demographic component was created to capture
characteristics of NP’s practice, including their location and type of practice, years of practice,
degree, age, gender, and ethnicity.
Rahim’s Organizational Conflict Inventory – II
The ROCI-II is available in three separate forms, noted A-B-C, and is different based on
the type of interpersonal conflict (manager/leader, subordinate, or peer) the participant is
evaluating. Form C, which is for evaluating peers, was used for this study (Appendix A). Form C
consists of 28 items, to which participants are prompted to rate their agreement on handling
interpersonal conflict with a peer using a 5-point Likert scale with only the endpoints labeled.
Each question has a response from 1 (strongly disagree) to 5 (strongly agree). Each question is
associated with one of the five different conflict management styles. Questions focus on
interpersonal interactions and conflict. The questionnaire is scored by adding the items and
dividing by the number of items for an average score for each style of interpersonal conflict
management (e.g., collaborative, accommodating, competing, avoiding, and compromising). The
style with the highest score indicates the individual’s interpersonal conflict management style.
The ROCI-II was designed to measure the five modes of interpersonal conflict
management. Factor analyses of data from a national sample of executives reflected the five

conflict management modes (Rahim, 1983). The five scales' test-retest and internal consistency
reliability coefficients are satisfactory and compare favorably with other instruments (Rahim,
1983). The discriminant analysis provides evidence of the empirical validity of the scales by
demonstrating five a priori dimensions of conflict management modes (Rahim, 1983).
Additionally, Rahim (1983) used two convenience samples to assess the scales’ reliability and
evaluate whether the scales were free from social desirability and response distortion bias.
Approximately 105 items were initially considered for inclusion. Confirmatory factor analysis
was used to reduce the number of items using item loadings below 0.40 as the criteria to exclude
an item. The final instrument contains 28 items, with seven items measuring each style.
Validity and Reliability. Construct validity and reliability were established and deemed
satisfactory (Rahim, 1983; Rahim & Magner, 1995). The final instrument contains 28 items with
factor loadings greater than or equal to .40. The selected factors represent the five independent
dimensions of conflict management. The intercorrelations among the five scales ranged between
-.03 and .33 (Rahim, 1983). Internal consistency of participant response (reliability) measured
using Cronbach’s alpha was satisfactory, with coefficient alphas ranging from .72-.77
(Integrating, Cronbach’s alpha = .77; Obliging, Cronbach’s alpha = .72; Dominating, Cronbach’s
alpha = .72; Avoiding, Cronbach's alpha = .75; Compromising, Cronbach's alpha = .72) and are
higher compared to the previous instruments. The test-retest correlation for the previous
instruments ranged from .14-.73, and test-retest reliabilities ranged from .60 and .83 (p < .0001)
(Rahim, 1983).
Team Learning and Psychological Safety Survey
In order to measure psychological safety, Amy Edmondson (1999) created the Team
Learning and Psychological Survey Scale (TLPS), which is valid and reliable. For this study,

only the PSS was used. The subscale contains seven items using a 7-point Likert scale with only
the endpoints labeled. Each question has a response ranging from 1 (very inaccurate) to 5 (very
accurate). The score ranges from 7 to 49 points. Participants are asked to answer each of the
seven questions from their current or recent team membership perspective. Three of the seven
questions are reversed scored.
Validity and Reliability. Edmondson’s (1999) TLPS is a 24-item survey using a 7-point
Likert scale. Measurable behaviors that are evaluated include task design, degree of
organizational support, team composition, team efficacy, team leader coaching, and
psychological safety. The PSS consists of 7 items, and the internal reliability of the subscale was
deemed satisfactory, Cronbach’s alpha = 0.82. All other group-level survey variables are
reported in the original 1999 article by Edmondson.
Tekleab et al.’s Conflict Management Success Subscale
Using a longitudinal approach, Tekleab et al. (2009) examined the relationship between
team conflict, conflict management, cohesion, and team effectiveness by examining 53 teams
(260 participants). The study aimed to evaluate if there was a direct and positive effect on team
cohesion and determine the relationship between two types of conflict -- relationship and team,
in addition to team cohesion. Tekleab et al. (2009) created a 28-item survey, Team Conflict,
Conflict Management (TCCM), to measure the construction of relationship conflict, task conflict,
conflict management, cohesion, perceived performance, team satisfaction, and team viability,
using a 7-point Likert scale. Responses range from 1 (never) to 7 (always).
The CMS subscale was used to evaluate perceived conflict management success. It most
closely aligns with individuals' conflict management styles (concern for self-versus concern for
others). The subscale contains four questions measured using a 7-point Likert scale with a total

subscale score ranging from 4 to 28. Participants are asked to answer each of the questions from
the perspective of their current or recent team. Additionally, for this study, two questions
measuring the construct of conflict management are combined with two questions adapted from
Cosier and Dalton (1990) to measure conflict management success.
Validity and Reliability. Tekleab et al.'s (2009) TCCM survey contains 28 questions
using a 7-point Likert scale. Measurable behaviors include relationship conflict, task conflict,
conflict management, cohesion, perceived performance, team satisfaction, and team viability.
The CMS subscale consists of four items, and the internal consistency (reliability) was deemed
satisfactory, Cronbach’s alpha = 0.79. All other group-level survey variables are reported in the
original 2009 article by Tekleab et al.
Data Collection and Analysis Procedures
Operational Definition of Variables
This study has three variables considered constructs: conflict management success,
interpersonal conflict management style, and psychological safety.
Conflict Management Success. Tekleab et al.'s (2009) CMS subscale was used to
evaluate conflict management success and is considered an interval-level dependent variable.
This subscale consists of four items on a 7-point Likert scale ranging from 1 (never) to 7
(always). Final scores range from 4 to 28 points. The higher the score, the greater the perception
of the team successfully managing conflict. CMS subscale scores are an outcome variable for
this study.
Interpersonal Conflict Management Style. Rahim’s (1983) ROCI-II was used to
evaluate the NP’s style of interpersonal conflict management and is reported as a nominal-level
independent variable. Five styles are reported: (a) avoiding, (b) dominating (competing), (c)

compromising, (d) obliging (accommodating), and (e) integrating (collaborating; Hocker &
Wilmot, 2018; Rahim, 1983).
This is a nominal level variable, represented by the subscale (i.e., interpersonal conflict
style) with the highest score. The conflict management style with the highest score was recorded
as the “primary” style. There are 28 items in the overall measure; participants responded to
prompts about conflict management on a 5-point Likert scale ranging from 1 (strongly disagree)
to 5 (strongly agree). Each question corresponds to one of the five styles of interpersonal conflict
management. For example, the avoiding style is measured by items 3, 6, 16, 17, 26, and 27.
Rahim (1983) used only the endpoints for each question in the survey. The questionnaire is
scored by adding the items for each category and dividing by the number of items for each
category to obtain a score for each style of interpersonal conflict management—scores for the
avoiding style range from 6 to 30. For the proposed study, interpersonal conflict management
style is an independent variable.
Psychological Safety. Psychological safety is measured by Edmondson's (1999) PSS
subscale and is considered an ordinal level of measurement. This scale consists of seven items
scored using a 7-point Likert scale with responses ranging from 1 (very inaccurate) to 7 (very
accurate) and is used to measure psychological safety. Final scores range from 7 to 49 points.
Questions 6 and 7 are reverse coded. The greater the positive response to the first five questions
and the greater the negative response to the last two questions, the stronger the perceived
psychological safety. Therefore, a score of 37 indicates the highest level of psychological safety,
and a score of 19 indicates the lowest level. Psychological safety is the dependent variable for
the first research question and a predictor variable for the second research question. According to

Harwell and Gatti (2001), Johnson and Creech (1983), Norman (2010), and Sullivan and Artino
(2013), ordinal-level data are treated as interval-level data.
Procedures
Qualified participants accessed the survey electronically through Qualtrics. Once the
screening questionnaire was completed and informed consent was obtained, noted by the
participant's digital signature, the survey was administered electronically. Each participant
completed a 54-item survey including the demographic questionnaire with descriptive questions
(15 items), Rahim's (1983) ROCI-II (28 items), Edmondson's PSS subscale (7 items), and
Tekleab et al.’s (2009) CMS subscale (4 items; Appendix A).
Participants did not have to answer each survey question and could skip questions they
felt uncomfortable answering (Appendix E). Upon completing the survey, the participant was
prompted with an exit screen noting that the survey was completed. Every participant was also
provided with my contact email address. The survey was open for ten weeks due to low
recruitment volumes.
Data Management
The email listserv used to recruit participants was de-identified before data collection was
initiated. Once data were collected, data were exported from Qualtrics into a two-factored
authentication-secured Excel spreadsheet. Statistical Package for the Social Sciences (SPSS) was
used for statistical analysis. Each participant had a unique identification number, and the data
were assessed for errors. Any errors in a single cell resulted in deleting that information, and the
cell was treated as missing data. Due to the potential effect of attrition, listwise deletion was only
used if the subject was missing more than 20% of their data.

Addressing missing data in the analysis is a complex issue, with multiple methods
currently accepted as best practices based on the missing data and data structure (Allison, 2001).
For example, listwise deletion removes all of a participant’s data from analysis but produces a
significant bias in estimation if the missingness is not entirely random. Since missing data
completely at random cannot be sufficiently proven, listwise deletion is never recommended to
address missing data. Multiple imputation is a group of methods that uses the remaining
information in the data set to estimate the most likely value of the missing data but can produce
unstable estimation if there is insufficient remaining information. The most appropriate method
is based on the structure of the data, which can only be determined after the data are collected.
Missing data, therefore, was addressed using an approach that matches the circumstance
(Allison, 2001; Baraldi & Enders, 2010; Enders, 2010; Little & Rubin, 2019).
Data Analysis
Data analysis occurred through multiple steps including: (a) data cleaning and missing
data analysis, (b) descriptive statistics and testing for assumptions, and (c) planned analysis to
answer research questions. Descriptive statistics (e.g., age, years of experience, gender, NP
specialty role, degree of autonomy [practice authority], and geographic location) were calculated.
The calculation included frequencies for categorical variables, measured central tendencies and
spread for continuous variables. The 95% confidence interval (95% CI) and effect size for a
given statistic are reported when possible (Tabachnick & Fidell, 2018).
RQ1. Are there statistically significant differences in scores for perceived psychological
safety based on the interpersonal conflict management style among NPs working in
interprofessional acute care or critical care teams in the United States?

For the first research question and hypotheses, Rahim's (1983) ROCI-II instrument was
used to calculate the participant's interpersonal conflict management raw score.
ANOVA Assumption Testing
● Assumptions of normality were evaluated by graphical and statistical means by
examining the shape and distribution of the data using a histogram and box plots, the
Skewness-Kurtosis test, and the Shapiro-Wilk test. In terms of using a histogram and box
plots, data are considered normal if the shape of the distribution is approximately
symmetrical and unimodal. The Skewness-Kurtosis tests for normality by examining the
skewness (i.e., asymmetry of distribution) and kurtosis (i.e., heaviness of a distribution
tail relative to a normal distribution; Cohen, 1988).
● Homoscedasticity was evaluated using Levene’s test. Levene's tests the null hypothesis
that the population variances are equal. If the p-value for Levene's test is greater than .05,
the variances are not significantly different, and the homogeneity assumption is met. On
the other hand, if the p-value for Levene's test is less than .05, there is potentially a
significant difference between the variances (Cohen, 1988; Tabachnick & Fidell, 2018).
Each ROCI-II subscale has a different number of survey items used to calculate the score.
This results in each scale having a different minimum and maximum score. Each participant was
classified into their dominant management style using the following steps:
1. The raw score for each conflict-handling style was computed by summing the responses
to the relevant items for that style and dividing by the number of items contributing to
that style, as described in the scoring instructions of the ROCI-II.
2. The average scores across the five conflict-handling styles were compared to determine
the participant's dominant style. The dominant style was the one with the highest average

score. For example, if a participant's average score for the integrating style was 3.73,
their average score for the obliging style was 2.54, their average score for the dominating
was 2.91, their average score for the avoiding style was 2.40, and their average score for
the compromising style was 3.05. Their dominant style was classified as an integrating
style.
3. The participant was classified as having a mixed dominant style if the average score was
the same across two or more styles. However, those who did not have a dominant style
(i.e., mixed, n = 95) were not included in the final analysis as Rahim's (1983) ROCI-II
did not have a "mixed" group, nor does he provide guidance on how to manage
participants who do not have a single dominant conflict management style.
Edmondson's (1999) TLPS was used to calculate the participant's degree of perceived
psychological safety.
A normal distribution has a skewness of zero and a kurtosis of three. The test is based on
the difference between the data's skewness and zero and the data's kurtosis and three. The test
rejects the hypothesis of normality when the p-value is less than or equal to .05. Failing the
normality allows you to state with 95% confidence that the data does not fit the normal
distribution. Passing the normality only allows you to state that no significant departure was
found. Similarly, the Shapiro-Wilk test is a statistical test of normality examining if the data
deviate from a comparable normal distribution. If the test is not significant (p > .05), the
distribution of the sample is not significantly different from the normal distribution (Tabachnick
& Fidell, 2018). A one-way Welch ANOVA was conducted to determine if there were
statistically significant differences in the degree of perceived psychological safety (dependent
variable) and the preferred interpersonal conflict management style (independent variable). A

one-way Welch ANOVA was selected as the best fit due to unequal variances as Welch's
ANOVA does not assume that variances are equal and allowed me to forego concern about the
assumption of homogeneous variances.
The assumption of linearity was tested by examining individual scatter plots for a linear
trend. Outliers were identified by creating residual scatter plots and determining values that fall
significantly from the central data cluster. An outlier was considered for removal if it occurred
away from the least squares line and exerted high leverage on the overall data pattern. Any
outliers removed were reported in the final ‘n’ of the model.
A Games-Howell Post Hoc test was completed to identify significant differences between
specific groups. Like the one-way Welch ANOVA, the Games-Howell post hoc test does not
require the groups to have equal standard deviation.
RQ2. How does psychological safety predict perceived conflict management success
among NPs working in interprofessional acute care or critical care teams in the United States?
Edmondson’s (1999) TLPS subscale scores were regressed onto the sum scores of
Tekleab et al.’s (2009) CMS subscale via a simple linear regression approach for the second
research question and hypotheses. A regression model was calculated to assess the influence of
CMS scores on TLPS.
Regression Assumptions:
● The assumption of linearity was tested by examining individual scatter plots for a linear
trend. Outliers were identified by creating residual scatter plots and determining values
that fall significantly from the central data cluster.

● An outlier was considered for removal if it occurred away from the least squares line and
exerted high leverage on the overall data pattern. Any outliers removed were reported
with the final ‘n’ of the model (Cohen, 1988; Tabachnick & Fidell, 2018).
● The assumption of homoscedasticity was considered met if a visual inspection of the
residual scatter plot showed an even distribution of data (Cohen, 1988; Tabachnick &
Fidell, 2018).
The appropriateness of the model will be assessed using the critical alpha value from the
F table and effect size using adjusted R2. If the model had acceptable explanatory power (p <
0.05), then the influence of the predictor was investigated using the standardized beta
coefficients. Continuous coefficients were interpreted as a one standard deviation increase in the
predictor, resulting in a weighted change in the outcome variable. The partial and semipartial
correlations were also used to evaluate the unique contribution of each predictor (Tabachnick &
Fidell, 2018).
Anticipated Challenges
Potential challenges to the study included the current severe acute respiratory syndrome
coronavirus 2 (SARS-CoV-2 aka COVID-19) pandemic, survey fatigue, and concern for the
inadvertent transmittal of protected health information. As COVID-19 remains a national health
emergency, NPs are finding themselves working in an ever-changing setting while enduring
hardships and challenges. Furthermore, before COVID-19, many health professionals, including
NPs, were experiencing survey fatigue. The anticipated challenges could be considered
limitations as well. The challenges were effectively managed by minimizing the number of
questions on the survey, allowing participants to complete the survey at intervals, and keeping

the recruitment window open longer. Careful attention was paid to ensure the survey did not
allow for receiving or transmitting protected health information (Phillips et al., 2018).
Researcher’s Role
I am an NP with a clinical practice in the upper Midwest of the United States. In order to
decrease the risk of research bias, various recruitment strategies were employed. For example, if
a participant who works for the same organization as me was recruited through either social
media or through one of the professional organizations and otherwise met the inclusion criteria,
they were allowed to participate in the survey. At the time of the study, I was not in a
supervisory position at my organization.
Ethical Considerations
Approval for the study was obtained from the Institutional Review Board (IRB) at
Abilene Christian University (IRB 2022-20). No data collection occurred until IRB approval was
obtained. The study qualified for exemption status under category II as the research only
involved survey procedures. The study conformed to the principles of the Belmont report,
including respect for persons, beneficence, and justice. Autonomy and the informed consent
process served as the ethical foundation for the study. Participants were provided extensive
information regarding the risks, benefits, and alternatives to participation via an informed
consent form. The survey showed minimal risk.
Furthermore, the survey contained an informed consent form with completion and a
digital signature indicating consent was obtained. Participants were then asked to complete the
survey voluntarily. There were no consequences for participating in the survey; participants
could contact me anytime to request withdrawal of their results (Polit & Beck, 2017).

Participant confidentiality and anonymity were maintained using several mechanisms.
Individuals were not asked to indicate their names; all data were de-identified, numerically
coded, and reported in aggregate (Polit & Beck, 2017). Results were reported in an anonymized
manner to avoid identifying participants or their organizations (Polit & Beck, 2017).
Furthermore, information obtained during this study was conducted in a manner so that the
identity of participants cannot readily be directly or indirectly ascertained. Any potential
disclosure of the participant's responses did not reasonably place the subjects at risk of criminal
or civil liability or result in damages to one's financial standing, employability, education,
advancement, or reputation.
While the research study involved NPs and the healthcare environment, the study did not
involve patient-identifiable information. No one other than myself and my dissertation chair can
access the data collected. Electronic data files are password-protected using two layered
authentications. All data are stored electronically or digitally on my computer and in a secured
cloud platform. Any printed information is stored in a locked cabinet when not being analyzed.
Abilene Christian University will retain all information for 3 years and be destroyed as outlined
by the university.
Regarding beneficence, the guiding principle is to do no harm and maximize benefits
while minimizing risks. The study contains minimal risk as the study was completed at the
participant’s convenience. Potential benefits of participating in the study include participants
exercising their autonomy and taking an active role in advancing their profession, advancing the
disciplines of organizational leadership and conflict management, and potentially improving
their professional environment. After the study, participants were invited to register for a chance
to receive a limited number of Amazon gift cards as a token of appreciation. A random number

generator, similar to one used for recruitment, was employed to choose the gift card recipients.
Individual anonymity and confidentiality were maintained throughout the study as personal
identifying information was removed, and the findings were reported in aggregate. As the study
used third-party management tools, including Qualtrics, there was a theoretical risk of breach of
email addresses or personal information retained on the participant's computer or electronic
device on behalf of third-party vendors. Participants were provided a link to the respective
privacy statements --Qualtrics -- https://www.qualtrics.com/support/survey-platform/getting-
started/data-protection-privacy/.
Further, IP addresses were not collected by the survey software. From a risk perspective,
the study did not introduce any known risk. Justice was ensured by carefully screening
participants and adhering to inclusion and exclusion criteria.
Assumptions
This study assumes some truths without the benefit of verification (Terrell, 2016). One
assumption is that participants are qualified to participate in the study. In order to address this
assumption, participants were required to complete a demographic questionnaire as a part of their
study. Another assumption is that participants provided candid, honest responses.
Limitations
Using the database for recruitment is a potential limitation of the study. The database
does not include every NP in the United States or its territories. However, obtaining email
contact is becoming increasingly challenging due to identity theft threats and restrictions
organizations must enact to protect their members (i.e., the General Data Protection Regulation).
Another potential limitation is the potential for self-selection bias. Participants who participate in
the survey may not provide accurate or complete information as they will be providing self-

reported responses, and they may alter their responses to create a sense of perceived
psychological safety and use of a collaborative style when managing interpersonal conflict.
The primary challenge or disadvantage to using quota sampling that is related to self-
selection bias is that the participants who function as a member of an interprofessional team and
who are choosing to participate in research when there is no significant benefit to them may have
different responses from those who do not function as a member of an interprofessional team or
choose not to participate (Muijs, 2011). As a result, the generalizability of the findings may be
limited due to sampling and self-selection bias.
Another potential limitation of the proposed study is my personal biases as an NP. I was
mindful of biases and avoided interpreting the data based on personal insights, hunches, or
intuitions (Leavy, 2017). Similarly, due to the current pandemic, many potential participants are
impacted by fatigue, creating potential recruitment and data collection challenges, which could
ultimately impact data analysis. NPs functioning on the frontline work more hours under austere
conditions and face hardships and other challenges. Additionally, many healthcare professionals,
including NPs, experience survey fatigue, particularly surveys with time constraints (Delva et al.,
2002). The anticipated limitations were mitigated by minimizing the number of questions on the
survey, allowing participants to complete the survey at their will by allowing them to exit and
return as needed using their link and keeping the recruitment window open longer. The study
was open to NPs practicing in the United States who otherwise meet inclusion criteria. Based on
the inherent nature of surveys, participants often feel limited by the range of responses and often
are limited to the text for direction regarding completing the survey (Delva et al., 2002). The
anticipated limitations were mitigated by providing explicit instruction, providing a manner in

which I could be contacted to extend the opportunity to either decline to answer a question or
provide responses to which the participant can respond.
Delimitations
The boundaries or delimitations of the study are discussed in the inclusion and exclusion
criteria, as noted above. One significant delimiting step is identifying and selecting the problem
of practice (Simon & Goes, 2013). The purpose of this quantitative correlational study was to
determine if there are differences in perceived psychological safety based on interpersonal
conflict management style and theorize how perceived psychological safety predicts perceived
conflict management success among NPs working in an interprofessional acute or critical care
team in the United States. While other professionals play a vital role in the interprofessional
healthcare team, the interpersonal conflict management style of providers other than NPs is
beyond the scope of this study. Another delimitation of the study is the decision to include
licensed NPs who practice in the United States and territories as opposed to opening recruitment
to NPs who practice outside of the United States. This decision reflects my recognition that NPs
in the United States healthcare system are restricted to the scope of practice mandated by the
state where they work. Other countries follow different governing rules and regulations, which
leads to different practice conditions that might not be generalizable to those within the United
States.
Furthermore, participants must have a minimum of 6 months of experience to be eligible
to participate in the study. The first 6 months after graduation from a professional program are
often spent writing the licensing exam, completing the hiring, obtaining licensing, and
completing initial onboarding processes. Thus, NPs within the first 6 months of practice might
not have enough relevant experience to comment on their perceptions of managing conflict

within an interprofessional care team. As a result, the results of this study will not be
generalizable to recent NP graduates with less than 6 months of practice experience.
Finally, this study focused on NPs who work in acute or critical care interprofessional
teams in the United States. Therefore, the results of this study may not be generalizable to NPs
who work in other types of interprofessional teams and care settings (e.g., specialty and
subspecialty teams outside of the acute and critical care setting).
Summary
Chapter 3 provides a detailed explanation of the research design and methods of a
nonexperimental, correlational, cross-sectional case study that evaluates the relationship between
the perceived psychological safety of the interpersonal acute/critical care team and the style of
interpersonal conflict management used by NPs who are a part of the interprofessional team. The
study includes NPs who are members of an acute or critical care team functioning as a part of an
interprofessional team. Three instruments, including Rahim's (1983) ROCI-II, Edmondson's
(1999) PSS subscale, and Tekleab et al.'s (2009) CMS subscale were used. Descriptive and
inferential statistics, including appropriate parametric/nonparametric testing and analysis based
on the data results, were conducted, and will be discussed further in Chapter 4.

Chapter 4: Results
The purpose of this quantitative, cross-sectional, correlational study was to examine if
there were differences in perceived psychological safety associated with interpersonal conflict
management style and to theorize how perceived psychological safety predicts perceived conflict
management success among nurse practitioners working in an interprofessional acute or critical
care team in the United States. Two research questions guided the study:
RQ1. How do scores for perceived psychological safety differ based on interpersonal
conflict management style among NPs working in interprofessional acute care or critical care
teams in the United States?
RQ2. How does psychological safety predict perceived conflict management success
among NPs working in interprofessional acute care or critical care teams in the United States?
Chapter 4 presents the findings of the data analysis and discussion of the demographic
characteristics of the study population, scoring, and reliability, confirmatory factor analysis, and
results specific to the above questions. Additionally, a secondary analysis examining the
relationship between gender and ethnicity in terms of perceived psychological safety and
interpersonal conflict management style is discussed.
Results
Demographic Characteristics
The study participants' demographic information was assessed using descriptive
statistical techniques. Frequencies (n) and percentages (%) of the sample characteristics are
presented in the following tables (Tables 1–4). A total of 981 participants completed the study.
However, two participants did not provide consent. An additional 35 participants were noted to
have zero variation in their response, raising concern that these responses were bot-driven, and

these results were subsequently removed. The final sample size for this study is 944 participants.
The majority of participants identified as female (n = 589, 62.4%) and White, non-Hispanic (n =
541, 57.3%), with the highest percentage of participants between the ages of 31 and 35 (n = 225,
23.8%). In terms of specialty, many of the participants identified as being either an adult-
gerontologic acute care nurse practitioner (AGACNP), an acute care nurse practitioner (ACNP-
BC, ACNP-C; n = 381, 40.4%), or an adult-gerontologic primary care nurse practitioner
(AGACNP)/adult nurse practitioner (ANP; n = 296, 31.3%). Likewise, many participants noted
that they work in an urban setting (n = 390, 41.3%) with an organizational size of 101–499 beds
(n = 415, 44%). Over 60% of participants reported working at a teaching/academic institution (n
= 589), and 56.1% (n = 530) noted that their primary facility was part of a health system. From a
practice authority perspective, nearly half of the participants (n = 470, 49.8%) noted working in a
full practice state. Geographically, the state with the most respondents who completed the survey
practice is California (n = 163, 17.3%). Other frequently reported states included Florida, 6.1%
(n = 58); Alabama, 5.4% (n = 51); and Minnesota 5.2% (n = 49). The states or territories with
the fewest participants included North Dakota, New Hampshire, Oklahoma, Puerto Rico, Rhode
Island, Virgin Island, Vermont, and Wyoming, each reporting 0.1% (n = 1).
Regarding experience and training, 31.4% of participants (n = 296) reported having
between 6 and 10 years of nursing experience as both a registered nurse and an advanced
practice registered nurse. Similarly, 32.7% of participants (n = 320) reported having between 6
and 10 years of experience as an advanced practice registered nurse (APRN). Interestingly,
29.2% (n = 276) of participants noted they received moderate conflict management training,
primarily through continuing nursing or medical education courses (n = 232, 24.6%). According
to the American Association of Nurse Practitioners (AANP), the demographic findings reflect

national statistics. More than 355,000 NPs are licensed to practice in the United States or
territories, with an average age of 46 years and an average of 9 years of experience (AANP,
2022). Similarly, a 2022 demographics research summary by Zippia found more than 213,000
licensed NPs employed in the United States, with 86.9% female and 13.1% male. The largest
ethnic population of NPs is Whites, at 77.0%, Hispanic/Latinos at 6.7%, Asians at 6.8%, and
Blacks/African Americans at 4.7%. According to Zippia (n.d.), the average age of the NP is 42
years. One of the reasons for the variance between AANP and Zippia is the lack of a centralized
data source. The findings of the AANP statistics come from a voluntary survey distributed
annually to members, schools, and employers. In contrast, Zippia obtains information from the
Bureau of Labor Statistics, the Census, and employment sites to cross-verify the information
from more than 30 million profiles. While the exact figures are unknown, it is reasonable to
assume that the findings are in the neighborhood of figures reported by the AANP and Zippia.
Table 1
Demographic Characteristics
Variable
n
%
Gender
Female
589
62.4
Male
326
34.5
Prefer not to answer
13
1.4
Transgender female
6
0.6
Not Listed
5
0.5
Transgender male
3
0.3
Gender variant/nonconforming
2
0.2
Ethnicity
White alone, non-Hispanic
541
57.3
American Indian and/or Alaska Native alone, non-Hispanic
122
12.9

Variable
n
%
Black or African alone, non-Hispanic
99
10.5
Hispanic
84
8.9
Asian alone, non-Hispanic
47
5.0
Native Hawaiian and other Pacific Islander alone, non-
Hispanic
27
2.9
Some other race alone, non-Hispanic
15
1.6
Multiracial, non-Hispanic
5
0.5
Prefer not to answer
4
0.4
Age range (years of age)
18–25
42
4.4
26–30
214
22.7
31–35
225
23.8
36–40
194
20.6
41–45
121
12.8
46–50
57
6.0
51–55
29
3.1
56–60
19
2.0
61–65
16
1.7
> 65
6
0.6
Prefer not to answer
21
2.2
Table 2
Nurse Practitioner Work Characteristics
Variable
n
%
Nurse Practitioner Specialty
Acute Care Nurse Practitioner (ACNP- BC, ACNP-C,
AGACNP)
381
40.4
Adult Nurse Practitioner (ANP and AGPCNP)
296
31.9
Gerontological Nurse Practitioner (GNP)
117
12.4
Variable
n
%
Family Nurse Practitioner (FNP)
112
11.9
Other
34
3.6
Prefer not to answer
4
0.4
Facility type
Urban
390
41.3
Rural
257
27.2
Critical access hospital
252
26.7
Not Listed
36
3.8
Prefer not to answer
9
0.9
Organization size
101–499 beds
415
44.0
More than (>) 500 beds
224
23.7
Less than (<) 100 beds
206
21.8
Not Listed
57
6.0
Unknown
23
2.4
Prefer not to answer
19
2.0
Teaching status
Teaching/academic
589
62.4
Non-teaching/non-academic
271
28.7
Unknown
60
6.4
Prefer not to answer
24
2.6
Health systems affiliated
Part of a health system
530
56.1
Independent owned
258
27.3
Unsure/unknown
110
11.7
Prefer not to answer
46
4.9
Ownership/Oversight
Local government (county, city, district) hospital
272
28.8
State government hospital
249
26.4
Privately owned hospital
209
22.1

Variable
n
%
Federal government
129
13.7
Unsure/unknown
61
6.5
Prefer not to answer
24
2.5
Practice Authority: Do you work in a state that is
considered:
Full Practice Authority
470
49.8
Reduced Practice Authority
212
22.5
Restricted Practice Authority
199
21.1
Unsure/unknown
37
3.9
Prefer not to answer
26
2.8
Table 3
Practice State/Territory
Practice state/territory
n
%
Practice state/territory
n
%
CA
163
17.3
NC
8
0.8
FL
58
6.1
NE
8
0.8
AL
51
5.4
NV
8
0.8
MN
49
5.2
HI
7
0.7
AR
46
4.9
OH
7
0.7
AS
44
4.7
ME
6
0.6
AK
42
4.4
UT
5
0.5
AZ
39
4.1
WA
5
0.5
CT
31
3.3
IA
4
0.4
NY
28
3
MT
4
0.4
CO
27
2.9
WV
4
0.4

Practice state/territory
n
%
Practice state/territory
n
%
LA
24
2.5
MH
3
0.3
TX
21
2.2
MO
3
0.3
DE
20
2.1
OR
3
0.3
MD
20
2.1
PA
3
0.3
KY
18
1.9
SC
3
0.3
KS
17
1.8
WI
3
0.3
MA
16
1.7
NM
2
0.2
IL
15
1.6
SD
2
0.2
ID
12
1.3
MP
1
0.1
IN
12
1.3
ND
1
0.1
NJ
12
1.3
NH
1
0.1
DC
11
1.2
OK
1
0.1
FM
11
1.2
PR
1
0.1
GA
11
1.2
RI
1
0.1
VA
11
1.2
VI
1
0.1
TN
10
1.1
VT
1
0.1
MI
9
1
WY
1
0.1
GU
8
0.8
Prefer not to answer
3
0.3
MS
8
0.8

Table 4
Experience and Training
Variable
n
%
Years of Professional Nursing Experience as both a RN and APRN
6 months–5 years
198
21.0
6–10 years
296
31.4
11–15 years
195
20.7
16–20 years
96
10.2
21–25 years
53
5.6
26–30 years
33
3.5
31–35 years
38
4.0
36–40 years
14
1.5
41–45 years
11
1.2
46–50 years
1
0.1
51 years or more
1
0.1
Prefer not to answer
8
0.8
Years of Professional Nursing Experience AS AN APRN
6 months–5 years
318
33.7
6–10 years
319
33.8
11–15 years
146
15.5
16–20 years
54
5.7
21–25 years
62
6.6
26–30 years
19
2.0

Variable
n
%
31–35 years
11
1.2
36–40 years
5
0.5
41–45 years
3
0.3
46–50 years
1
0.1
51 years or more
1
0.1
Prefer not to answer
5
0.5
Previous Conflict Management Training
Extensive training
170
18.0
Little training
182
19.3
Moderate training
276
29.2
None
47
5.0
Prefer not to answer
12
1.2
Some training
257
27.2
Sources of Conflict Management Training
Employer provided training
241
25.5
Continuing Nursing/Medical Education
232
24.6
Received training in your NP program
225
23.8
Obtained through professional association
135
14.3
Self-selected/self-taught
82
8.7
Prefer not to answer
16
1.7
Other
13
1.4

Scoring and Reliability
Confirmatory Factor Analysis (CFA) for Validating Adapted Survey Scales
Confirmatory factor analysis (CFA) is a statistical technique commonly used to assess the
construct validity of measurement instruments. In this study, we aimed to validate the results of
two survey scales Edmondson's (1999) PSS subscale and Tekleab et al.'s (2009) CMS subscale
that initially used 7-point Likert scales, but for the study, were inadvertently changed to 5-point
Likert scales. Given the change in response options, assessing whether the adapted survey scales
still measure the same constructs as the original scales is essential. Therefore, CFAs were
conducted to confirm that the factor structure of the adapted scales is consistent with the original
scales and to examine the scales' validity in measuring the constructs of interest. The findings of
the CFAs are presented below.
Psychological Safety Subscale
The CFA assessed the measurement model of the seven-item PSS subscale using the one-
factor solution proposed by Edmondson (1999) using maximum likelihood estimation. The
confirmatory factor analysis used all seven items in Edmondson's original scale development
article (1999). Although Edmondson (1999) does not explicitly define the reverse scoring
necessary in the scale, as the items are not all phrased in the same direction (items 1, 3, and 5 are
positively phrased while others are negatively phrased), items 1, 3, and 5 were reverse scored
before conducting the CFA. All seven items had a standardized coefficient between -.68 and .66,
with all items being significant with a p < .05. The coefficient estimates indicated that all
psychological safety items significantly loaded on the psychological safety factor.
While the alpha level of the PSS subscale is concerning at 0.50, falling below the
conventional threshold of 0.70, one needs to consider the specific context of the research setting,

and the decision was made to proceed with the full seven-item scale while acknowledging the
limitation of low reliability. Adhering to the original scale ensures alignment with Edmondson's
(1999) conceptualization, promoting consistency and enhancing the study's validity by assessing
the construct as designed. Additionally, preserving the integrity of the measure by not modifying
it further (i.e., aside from the inadvertent change in the Likert scale) maintains continuity with
previous research that used Edmondson's (1999) scale, which facilitates comparison with prior
studies, promotes replicability of findings and contributes to the growing body of knowledge of
psychological safety and conflict management.
Conflict Management Success Subscale
The results of the confirmatory factor analysis (CFA) for conflict management success
indicate a significant positive relationship between the latent construct conflict management
success (CMS) and each of the four CMS items. The results showed that all four observed
variables had significant positive loadings on CMS with coefficients ranging from .52 to .74, all
p < .001. CFAs and Cronbach's alpha were used to assess the validity and reliability of two
survey scales measuring psychological safety and conflict management success. The results of
the CFA confirmed that the adapted survey scale of CMS maintained the same factor structure as
the original scale, indicating adequate construct validity.
Table 5 summarizes the seven constructs' internal reliability (Cronbach’s alpha). The
reliability of the study measures was assessed using Cronbach's alpha coefficient. All values
exceeded the recommended threshold of 0.7, as Hair et al. (2013) provided, except psychological
safety, which measured at .50.

Table 5
Internal Reliability
Construct
No. of items
α
Psychological Safety Survey (PSS) Subscale
Psychological safety subscale
7
.50
Team Conflict, Conflict Management Success (CMS) Subscale
Conflict Management Success subscale
4
.73
Rahim’s Organizational Conflict Inventory – II (ROCI-II)
Collaborating Style (integrating)
7
.86
Accommodating Style (obliging)
6
.74
Competing Style (dominating)
5
.76
Avoiding Style
6
.76
Compromising Style
4
.70
Classification of Conflict Management Styles
Each participant was classified into their dominant management style using the following
steps:
1. The raw score for each conflict-handling style was computed by summing the responses
to the relevant items for that style and dividing by the number of items contributing to
that style, as described in the scoring instructions of Rahim’s Organizational Conflict
Inventory–II.
2. The average scores across the five conflict-handling styles were compared to determine
the participant's dominant style. The dominant style was the one with the highest average
score. For example, if a participant's average score for the integrating style was 3.73,
their average score for the obliging style was 2.54, their average score for the dominating
was 2.91, their average score for the avoiding style was 2.40, and their average score for
the compromising style was 3.05. Their dominant style was classified as an integrating
style.
3. The participant was classified as having a mixed dominant style if the average score was
the same across two or more styles. The mixed category is reported for descriptive
purposes but is excluded from further analysis as Rahim's (1983) ROCI-II and research
do not account for mixed style.
Table 6 summarizes the frequencies and percentages of participants by their dominant
conflict management style.
Table 6
Conflict Management Style
Baseline characteristic
n
%
Integrating
292
30.9
Obliging
123
13.0
Dominating
133
14.1
Avoiding
93
9.9
Compromising
208
22.0
Mixed*
95
10.1
Note. *excluded from further analysis.
Most participants (30.9%) were classified as integrating conflict management style, and
the least (9.9%) classified the avoiding style. The compromising and dominating styles were also
frequently reported, with 22.0% and 14.1% of participants classified as these, respectively. The

obliging and mixed styles were less commonly reported, with 13.0% and 10.1% of participants
endorsing these styles, respectively. The mixed category is excluded from further analysis as
Rahim's (1983) ROCI-II and research do not account for mixed style. Table 7 contains a
summary of findings for the descriptive statistics of the composite scores of the seven constructs.
Table 7
Descriptive Statistics of the Seven Composite Constructs
Instruments
M*
SD
SEM
Min
Max
Skewness
Kurtosis
Psychological Safety (PSS)
Psychological Safety
3.24
0.55
0.02
1
5
0.49
2.19
Team Conflict, Conflict Management (CMS)
Conflict Management Success
3.46
0.77
0.03
1
5
-0.33
0.26
Rahim’s Organizational Conflict Inventory – II (ROCI-II)
Collaborating Style (integrating)
3.72
0.75
0.02
1
5
-0.29
0.02
Accommodating Style (obliging)
3.48
0.66
0.02
1
5
-0.17
0.23
Competing Style (dominating)
3.31
0.78
0.03
1
5
-0.37
0.23
Avoiding Style
3.36
0.72
0.02
1
5
-0.19
0.23
Compromising Style
3.63
0.71
0.02
1
5
-0.33
0.31
Note.*All mean scores are based on a Likert scale of 1 (low) to 5 (high). The possible mean
range for each construct is 1 to 5. N = 944.
The ROCI-II was used to measure five conflict-handling styles: integrating (M = 3.72, SD
= 0.75), obliging (M = 3.48, SD = 0.66), dominating (M = 3.31, SD = 0.78), avoiding (M = 3.36,
SD = 0.72), and compromising (M = 3.63, SD = 0.71). Skewness values ranged from -0.17 to -

0.37, indicating a slightly negative deviation from normal distribution, while kurtosis values
ranged from 0.02 to 0.31, indicating a relatively flat peak. The PSS and CMS skewness values
were 0.49 and -0.33, respectively, and kurtosis values were 2.19 and 0.26, respectively.
Results Specific to Research Questions
Research Question #1
Are there statistically significant scores for perceived psychological safety differences
based on the interpersonal conflict management style among NPs working in interprofessional
acute care or critical care teams in the United States? Participants were classified into five
groups: (a) integrating (n = 291), (b) obliging (n = 123), (c) dominating (n = 133), (d) avoiding (n
= 93), and (e) compromising (n = 208). Those who did not have a dominant style (i.e., mixed, n
= 95) were not included in the analysis as Rahim's (1983) ROCI-II did not have a "mixed" group,
nor does he provide guidance on how to manage participants who do not have a primary conflict
management style. Additionally, while outliers were present, after the removal of the outliers, the
results remained unchanged, and thus, they were retained in the analysis. Data were not normally
distributed for each group, as assessed by the Shapiro-Wilk test (p < .05), and there was a
heterogeneity of variances, as assessed by Levene's Test for Homogeneity (p < .001). However,
the Shapiro-Wilk test is not recommended for sample sizes larger than 50 as it considers slight
deviations from normality statistically significant. Generally, one-way ANOVA is robust to
deviations from normality, especially when the sample sizes are similar in each group (Lix et al.,
1996). Even somewhat skewed distributions are not always problematic if sample sizes are large.
If the distributions of each group are equally skewed, they are not problematic (Sawilowsky &
Blair, 1992). Therefore, a one-way Welch ANOVA was conducted to determine scores for
perceived psychological safety based on the interpersonal conflict management style among NPs

working in interprofessional acute care or critical care teams in the United States. The means,
standard deviations, and standard errors of the perceived psychological safety scores per conflict
management style, as well as results of the one-way Welch ANOVA, are presented in Table 8.
Table 8
Descriptive Statistics Comparing Perceived Psychological Safety Scores Across Conflict
Management Styles
Conflict management style
n
Psychological safety
M
SD
SE
Integrating
292
3.49
0.67
0.04
Obliging
123
3.02
0.44
0.04
Dominating
133
3.11
0.39
0.03
Avoiding
93
3.09
0.41
0.04
Compromising
208
3.12
0.35
0.02
A one-way Welch ANOVA was conducted to determine if there are statistically
significant differences in scores for perceived psychological safety based on the interpersonal
conflict management style among NPs working in an interprofessional acute care or critical care
team in the United States. The results indicated a statistically significant difference, F(4, 338.97)
= 22.78, p < .001; therefore, a Games-Howell post-hoc analysis was conducted. The findings of
the Games-Howell post hoc test are outlined in Table 9.

Table 9
Games-Howell Post Hoc Tests
Conflict management style
Mean difference
p
Integrating
Obliging
.47
< .001
Dominating
.38
< .001
Avoiding
.40
< .001
Compromising
.37
< .001
Obliging
Integrating
-.47
< .001
Dominating
-.09
0.454
Avoiding
-.07
0.757
Compromising
-.10
0.197
Dominating
Integrating
-.38
< .001
Obliging
.09
0.454
Avoiding
.02
0.998
Compromising
-.01
0.998
Avoiding
Integrating
-.40
< .001
Obliging
.07
0.757
Dominating
-.02
0.998
Compromising
-.03
0.97
Compromising
Integrating
-.37
< .001
Obliging
.10
0.197
Dominating
.01
0.998
Avoiding
.03
0.97
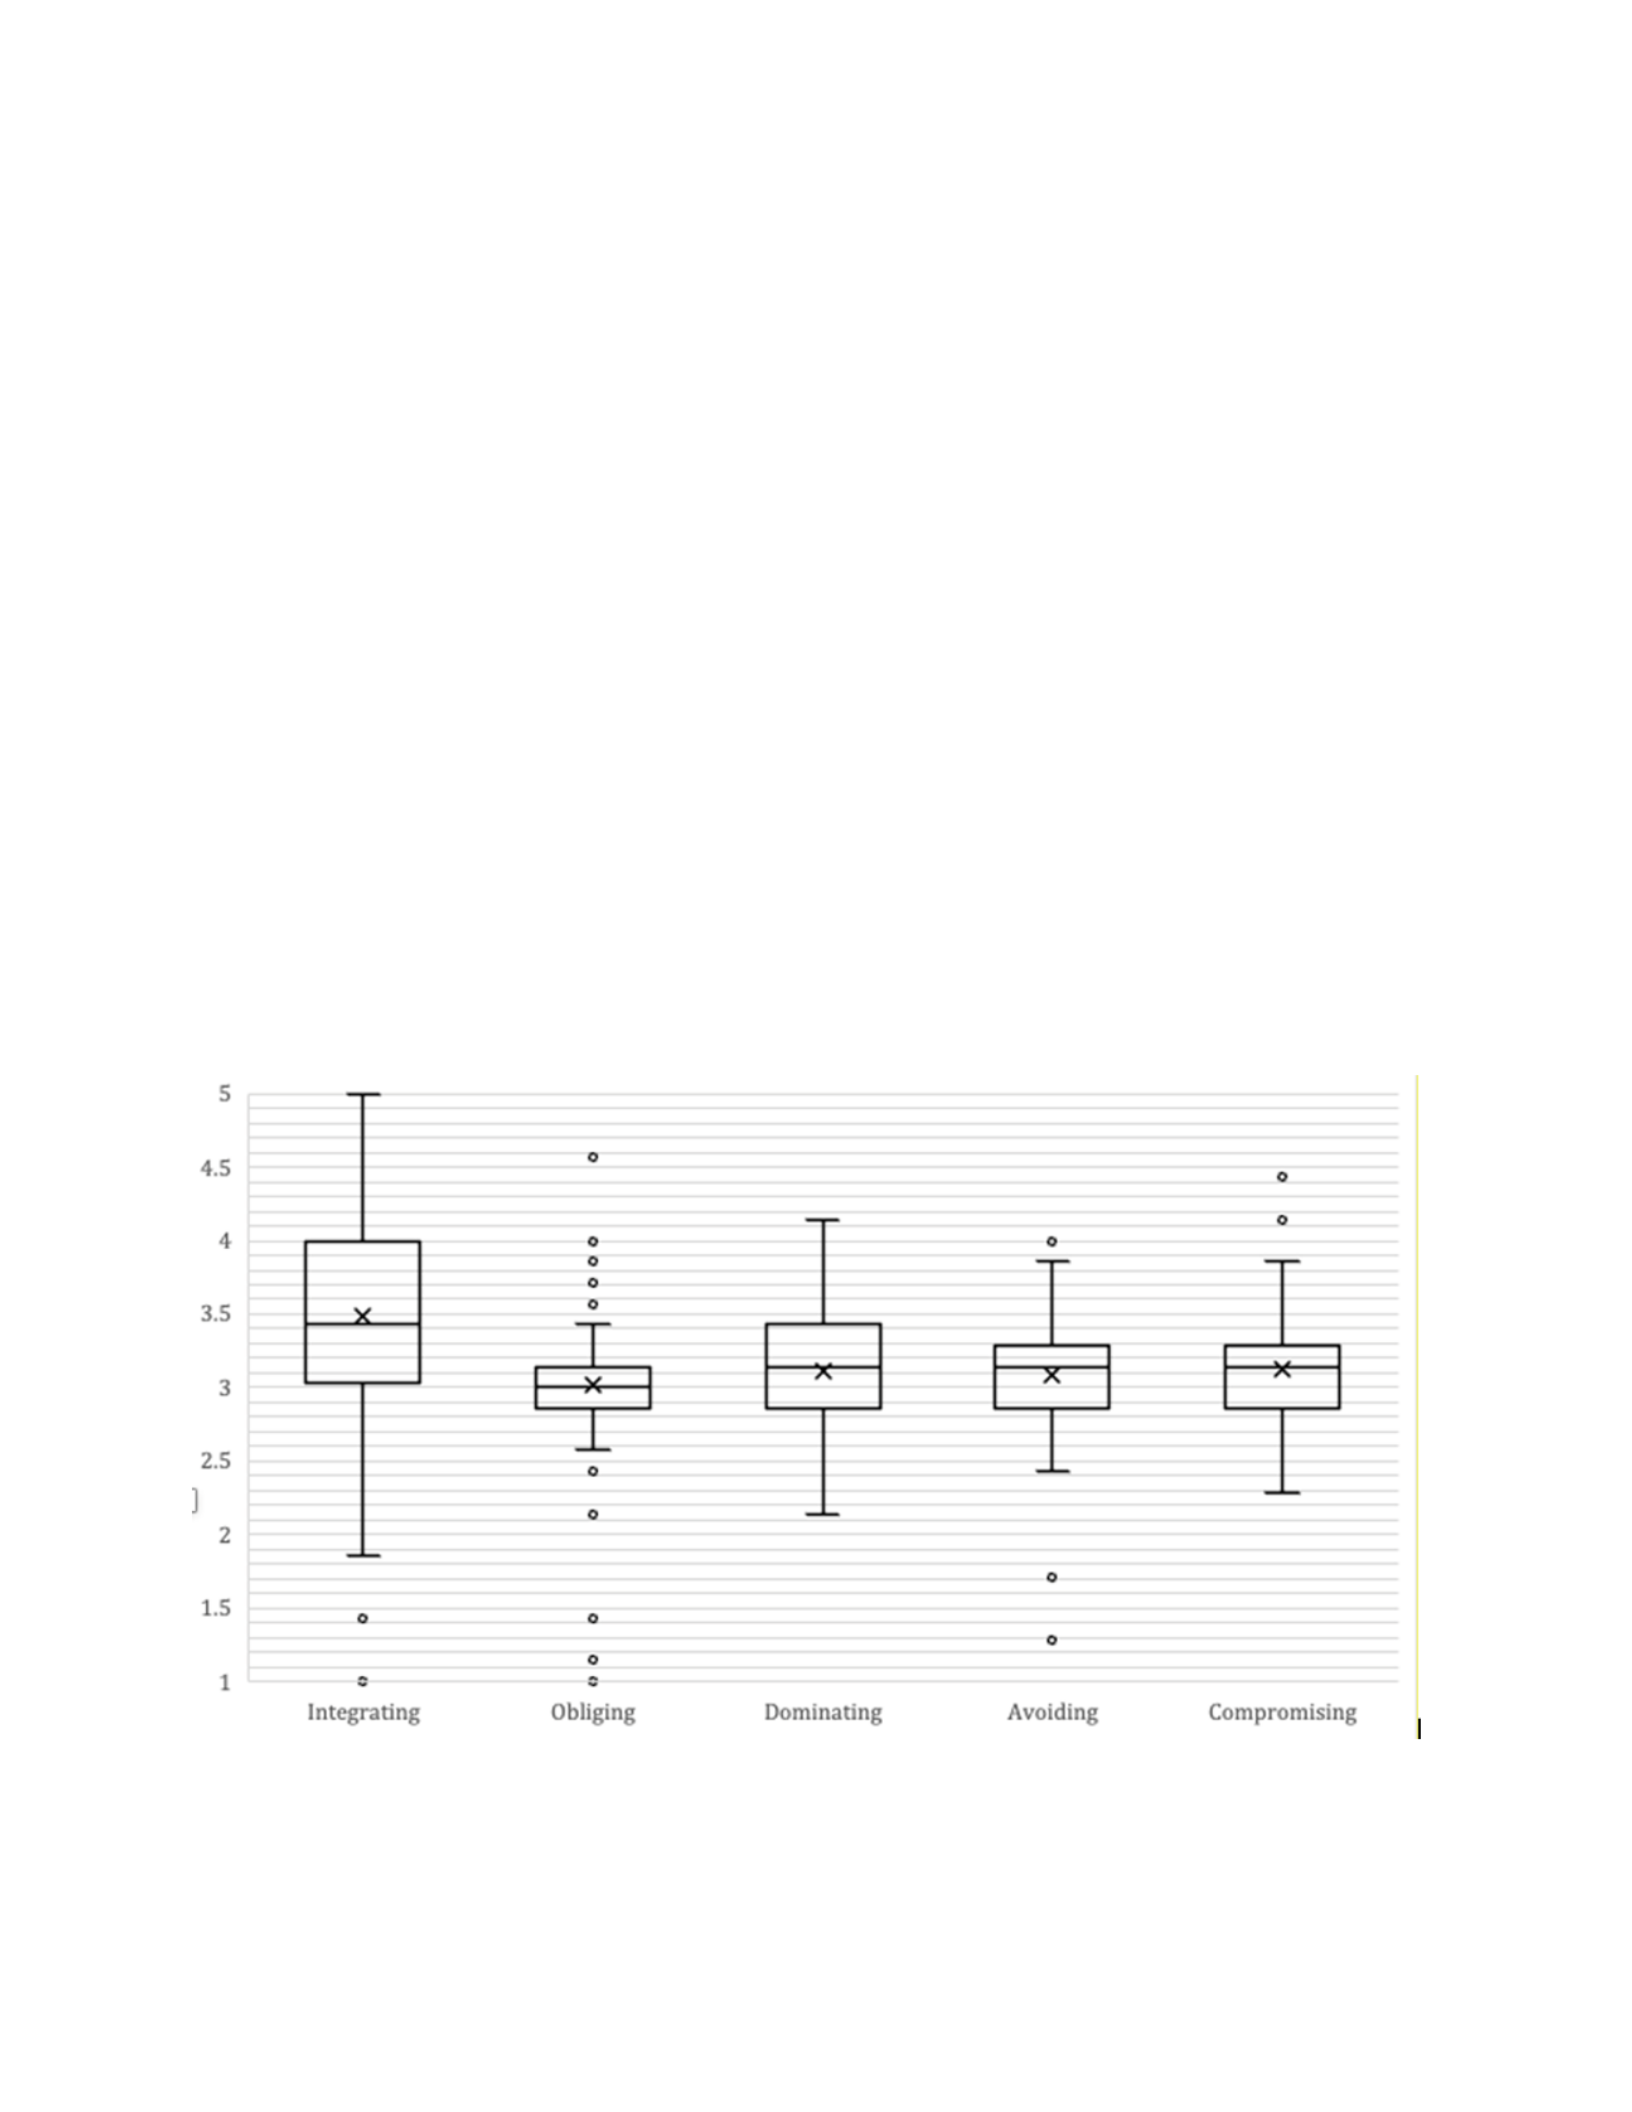
As shown in Figure 2, Games-Howell post hoc tests revealed that the mean level of
psychological safety was significantly higher for the integrating style (M = 3.49, SD = 0.67)
when compared to the obliging style (M = 3.02, SD = 0.44), dominating style (M = 3.11, SD =
0.39), avoiding style (M = 3.09, SD = 0.41), and compromising style (M = 3.12, SD = 0.35) with
all p values < .001. Although the mean levels of psychological safety for obliging, dominating,
avoiding, and compromising styles were significantly lower than integrating, they did not
significantly differ from each other (all p values > .05). These results suggest that the conflict
management style used by NPs may have an impact on the psychological safety perceptions of
the interprofessional team that they are a part of, with integrating conflict management style
resulting in the highest mean level of psychological safety.
Figure 2
Distribution of Psychological Safety Scores per Conflict Management Style

Conflict Management Style
Research Question #2
How does psychological safety predict perceived conflict management success among
NPs working in interprofessional acute care or critical care teams in the United States? The
following needs to be assessed before proceeding with interpreting the results of a simple linear
regression: (a) unusual observations/outliers, (b) interpreting linearity, (c) testing for
homoscedasticity, and (d) checking for normality.
Unusual Observations/Outliers. Five observations had standardized residuals greater
than 3 when included in the regression models. These were removed, and the regression model
ran again, although three new outliers appeared given the updated model. The model's results did
not change given the inclusion vs exclusion of outliers; therefore, they were retained in the data
set for analysis.
Interpreting Linearity. Interpreting linearity was satisfied, as established by the
significant correlation between TLPS and CMS in Table 8 and the visual inspection of the
scatterplot in Figure 3.
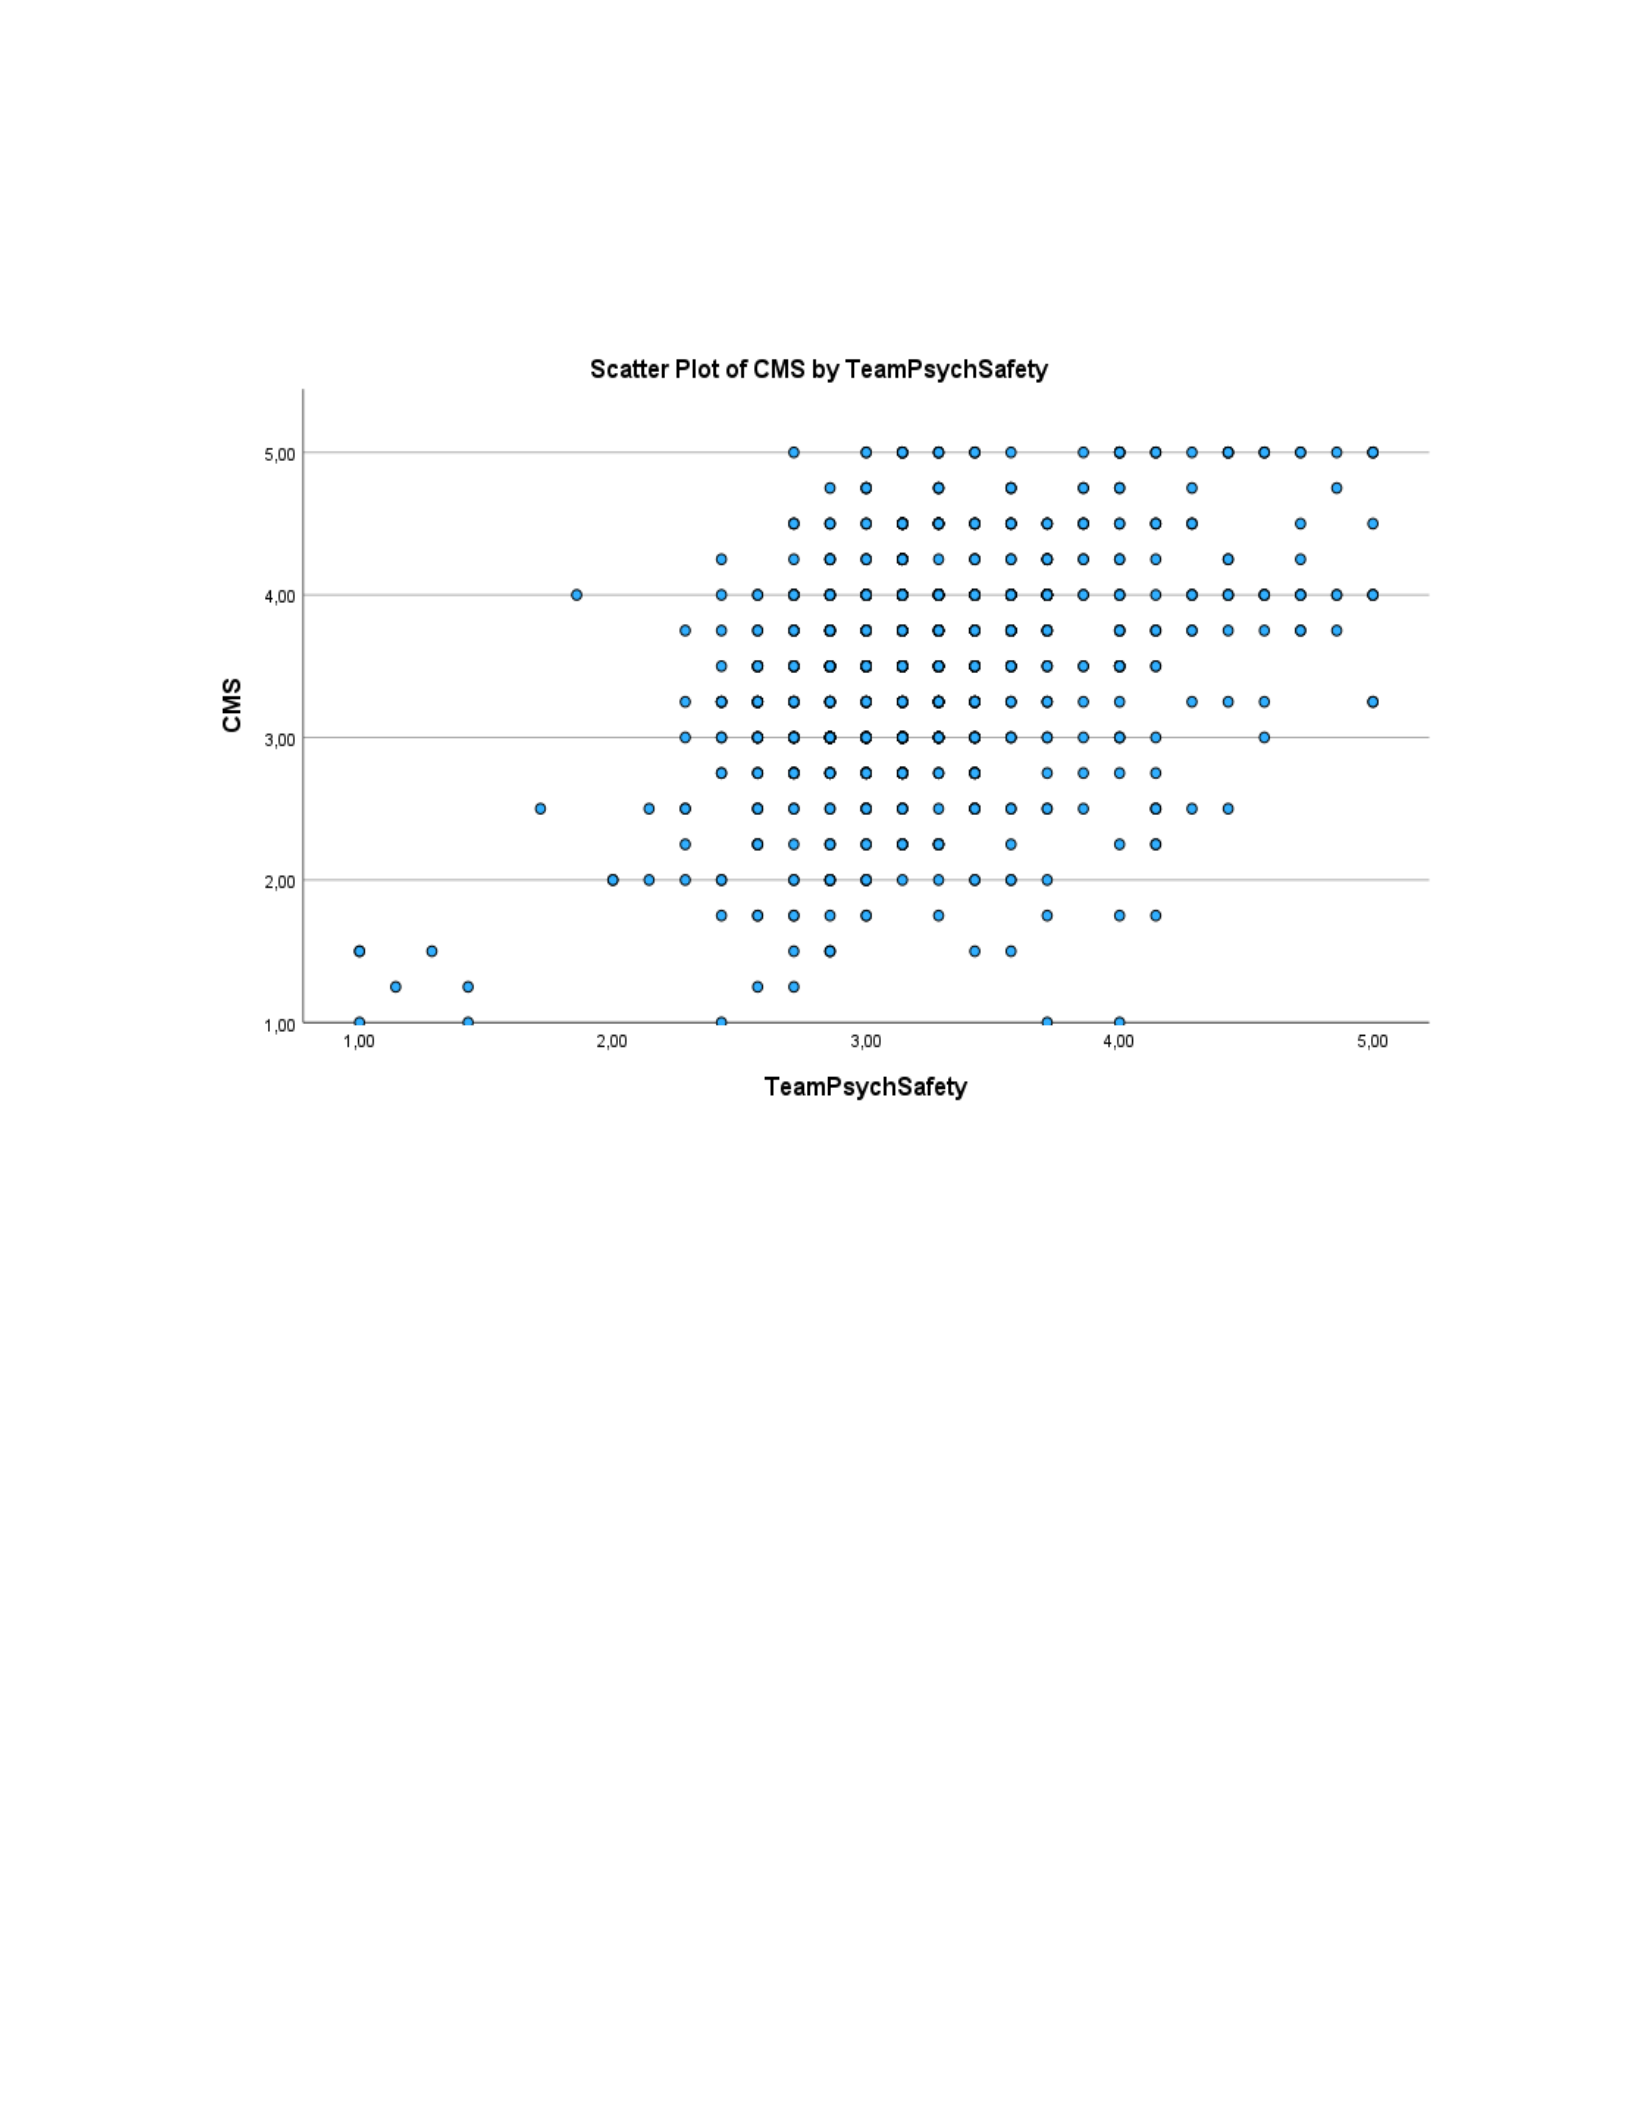
Figure 3
Scatterplot of Conflict Management Success by Psychological Safety
Testing for Homoscedasticity. Testing for homoscedasticity is assessed by visual
inspection of a plot of standardized residuals versus standardized predicted values in Figure 4. If
there is homoscedasticity, the spread of the residuals will not increase or decrease as the
predicted values increase. There was approximate homoscedasticity as demonstrated in Figure 4
with better performance at lower and higher values of the predictor.
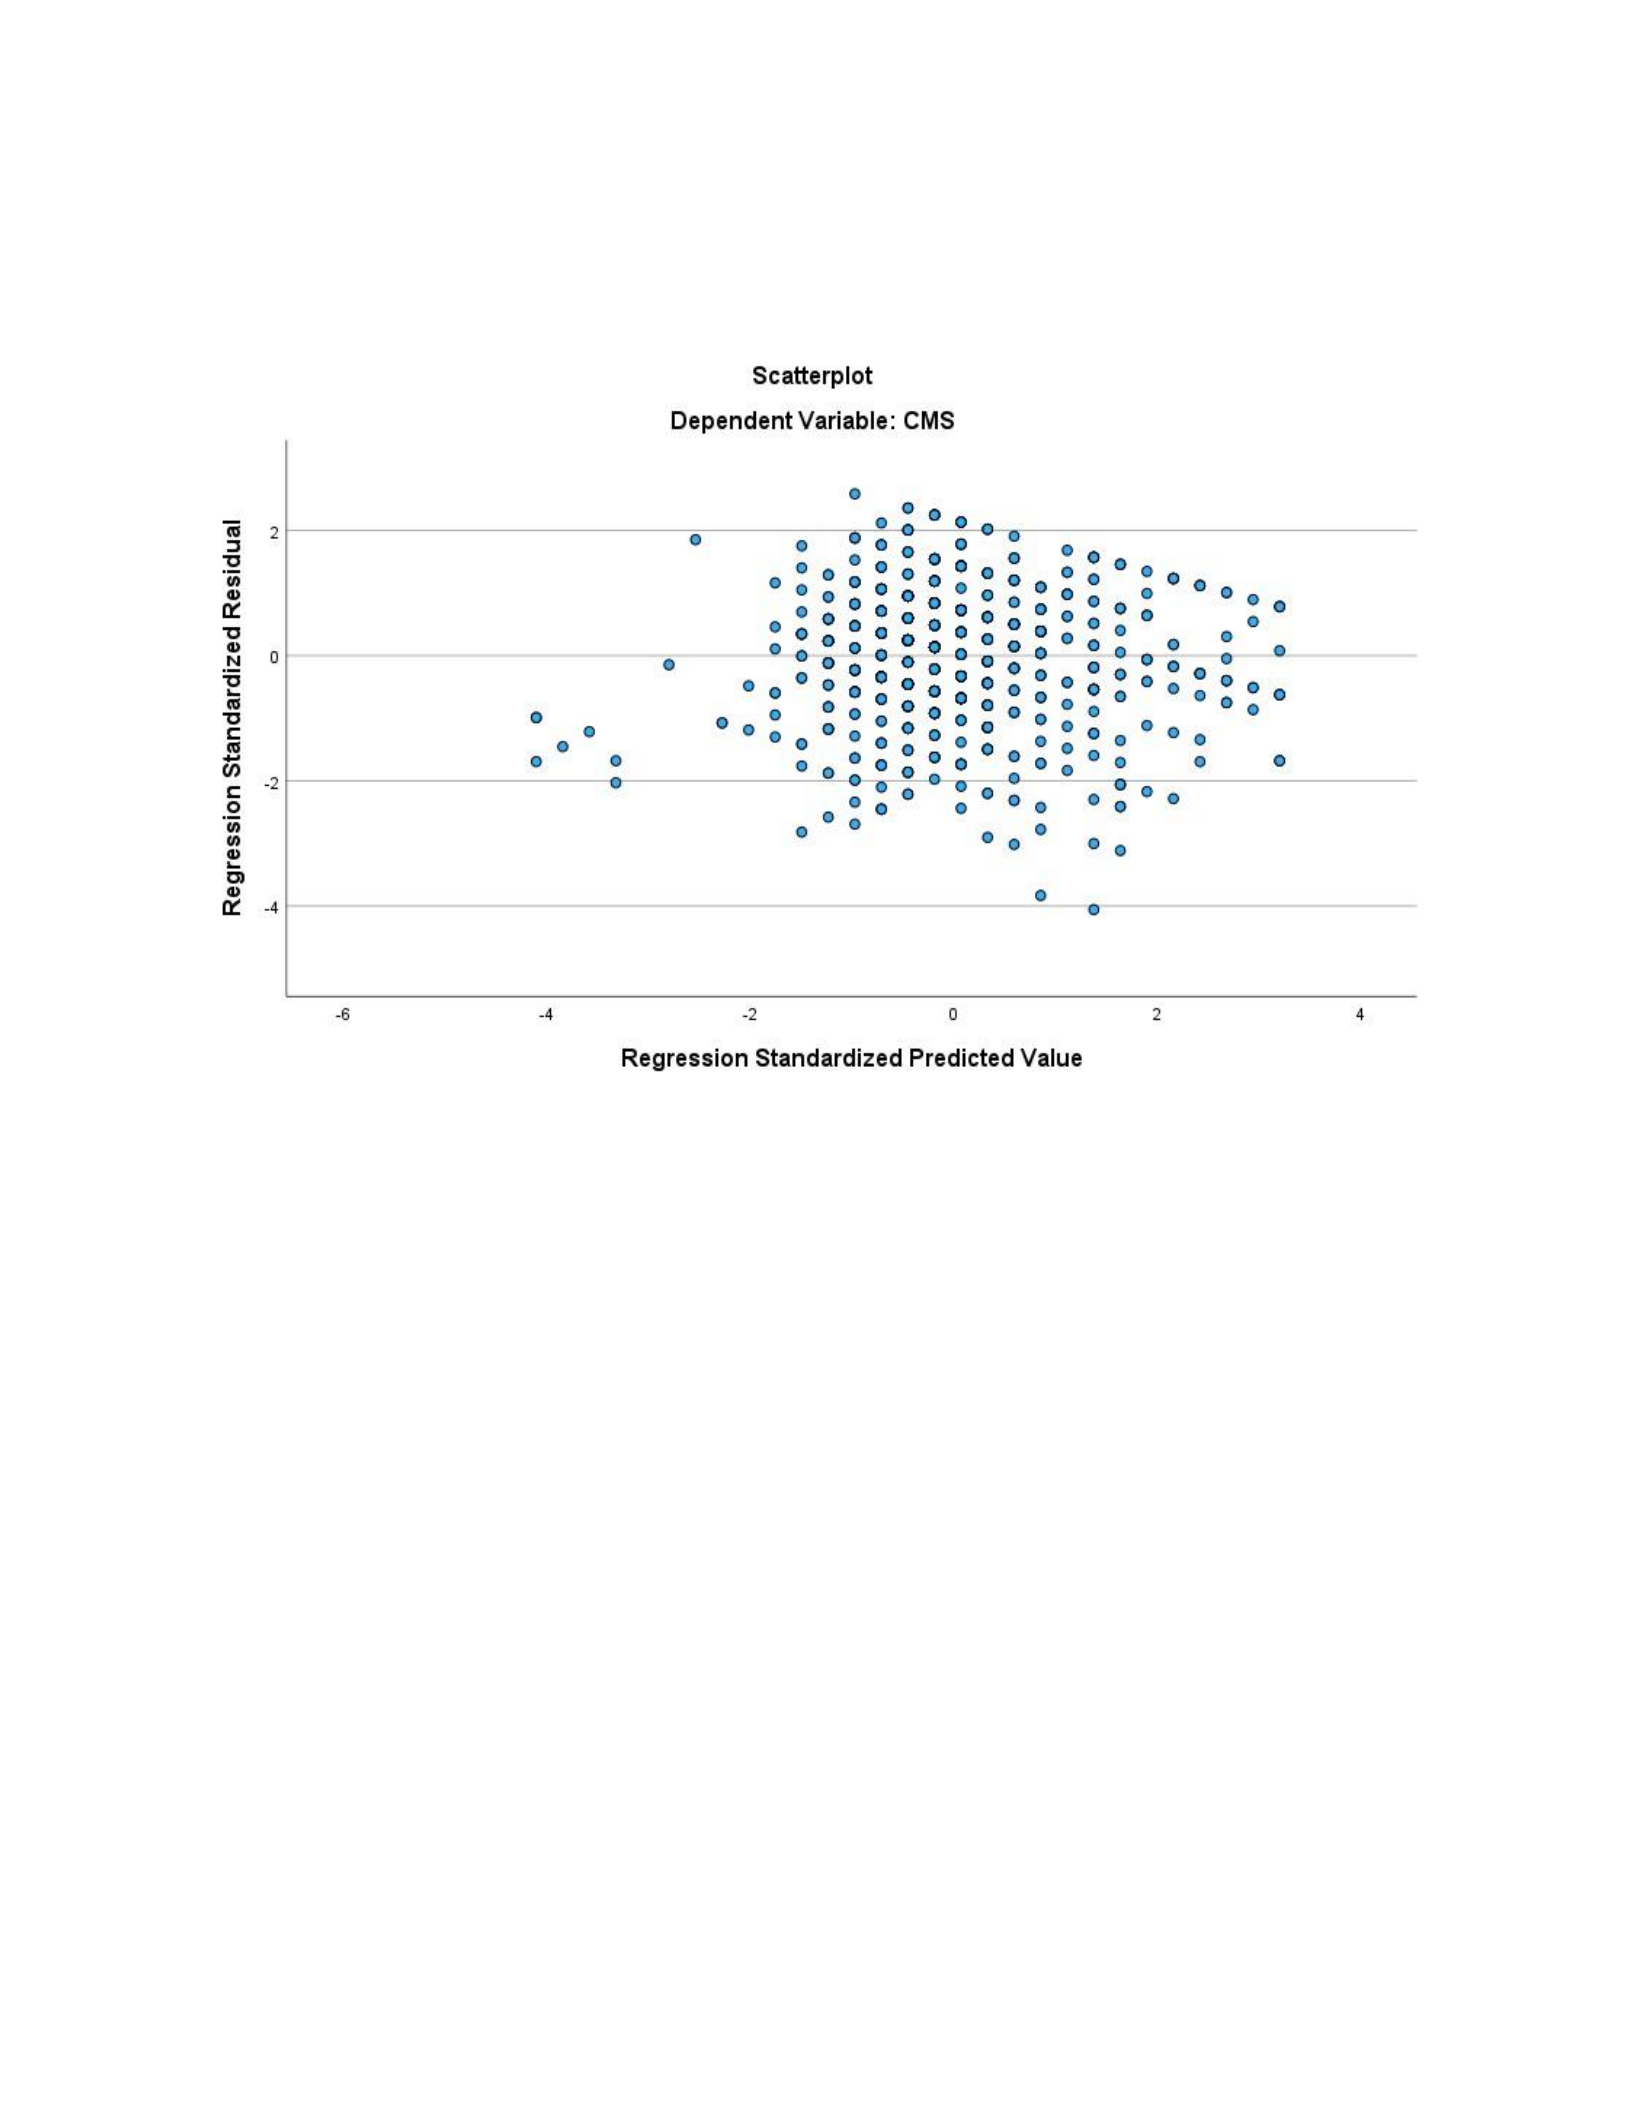
Figure 4
Standardized Residuals Versus Standardized Predicted Values
Checking for Normality. Checking for normality is assessed by visually examining a
histogram of the standardized residuals and a normal P-P plot in Figure 5. The mean and
standard deviation values are approximately 0 and 1, respectively. The residuals are
approximately normally distributed, as assessed by the points falling roughly along the diagonal
line on the normal P-P plot in Figure 5.
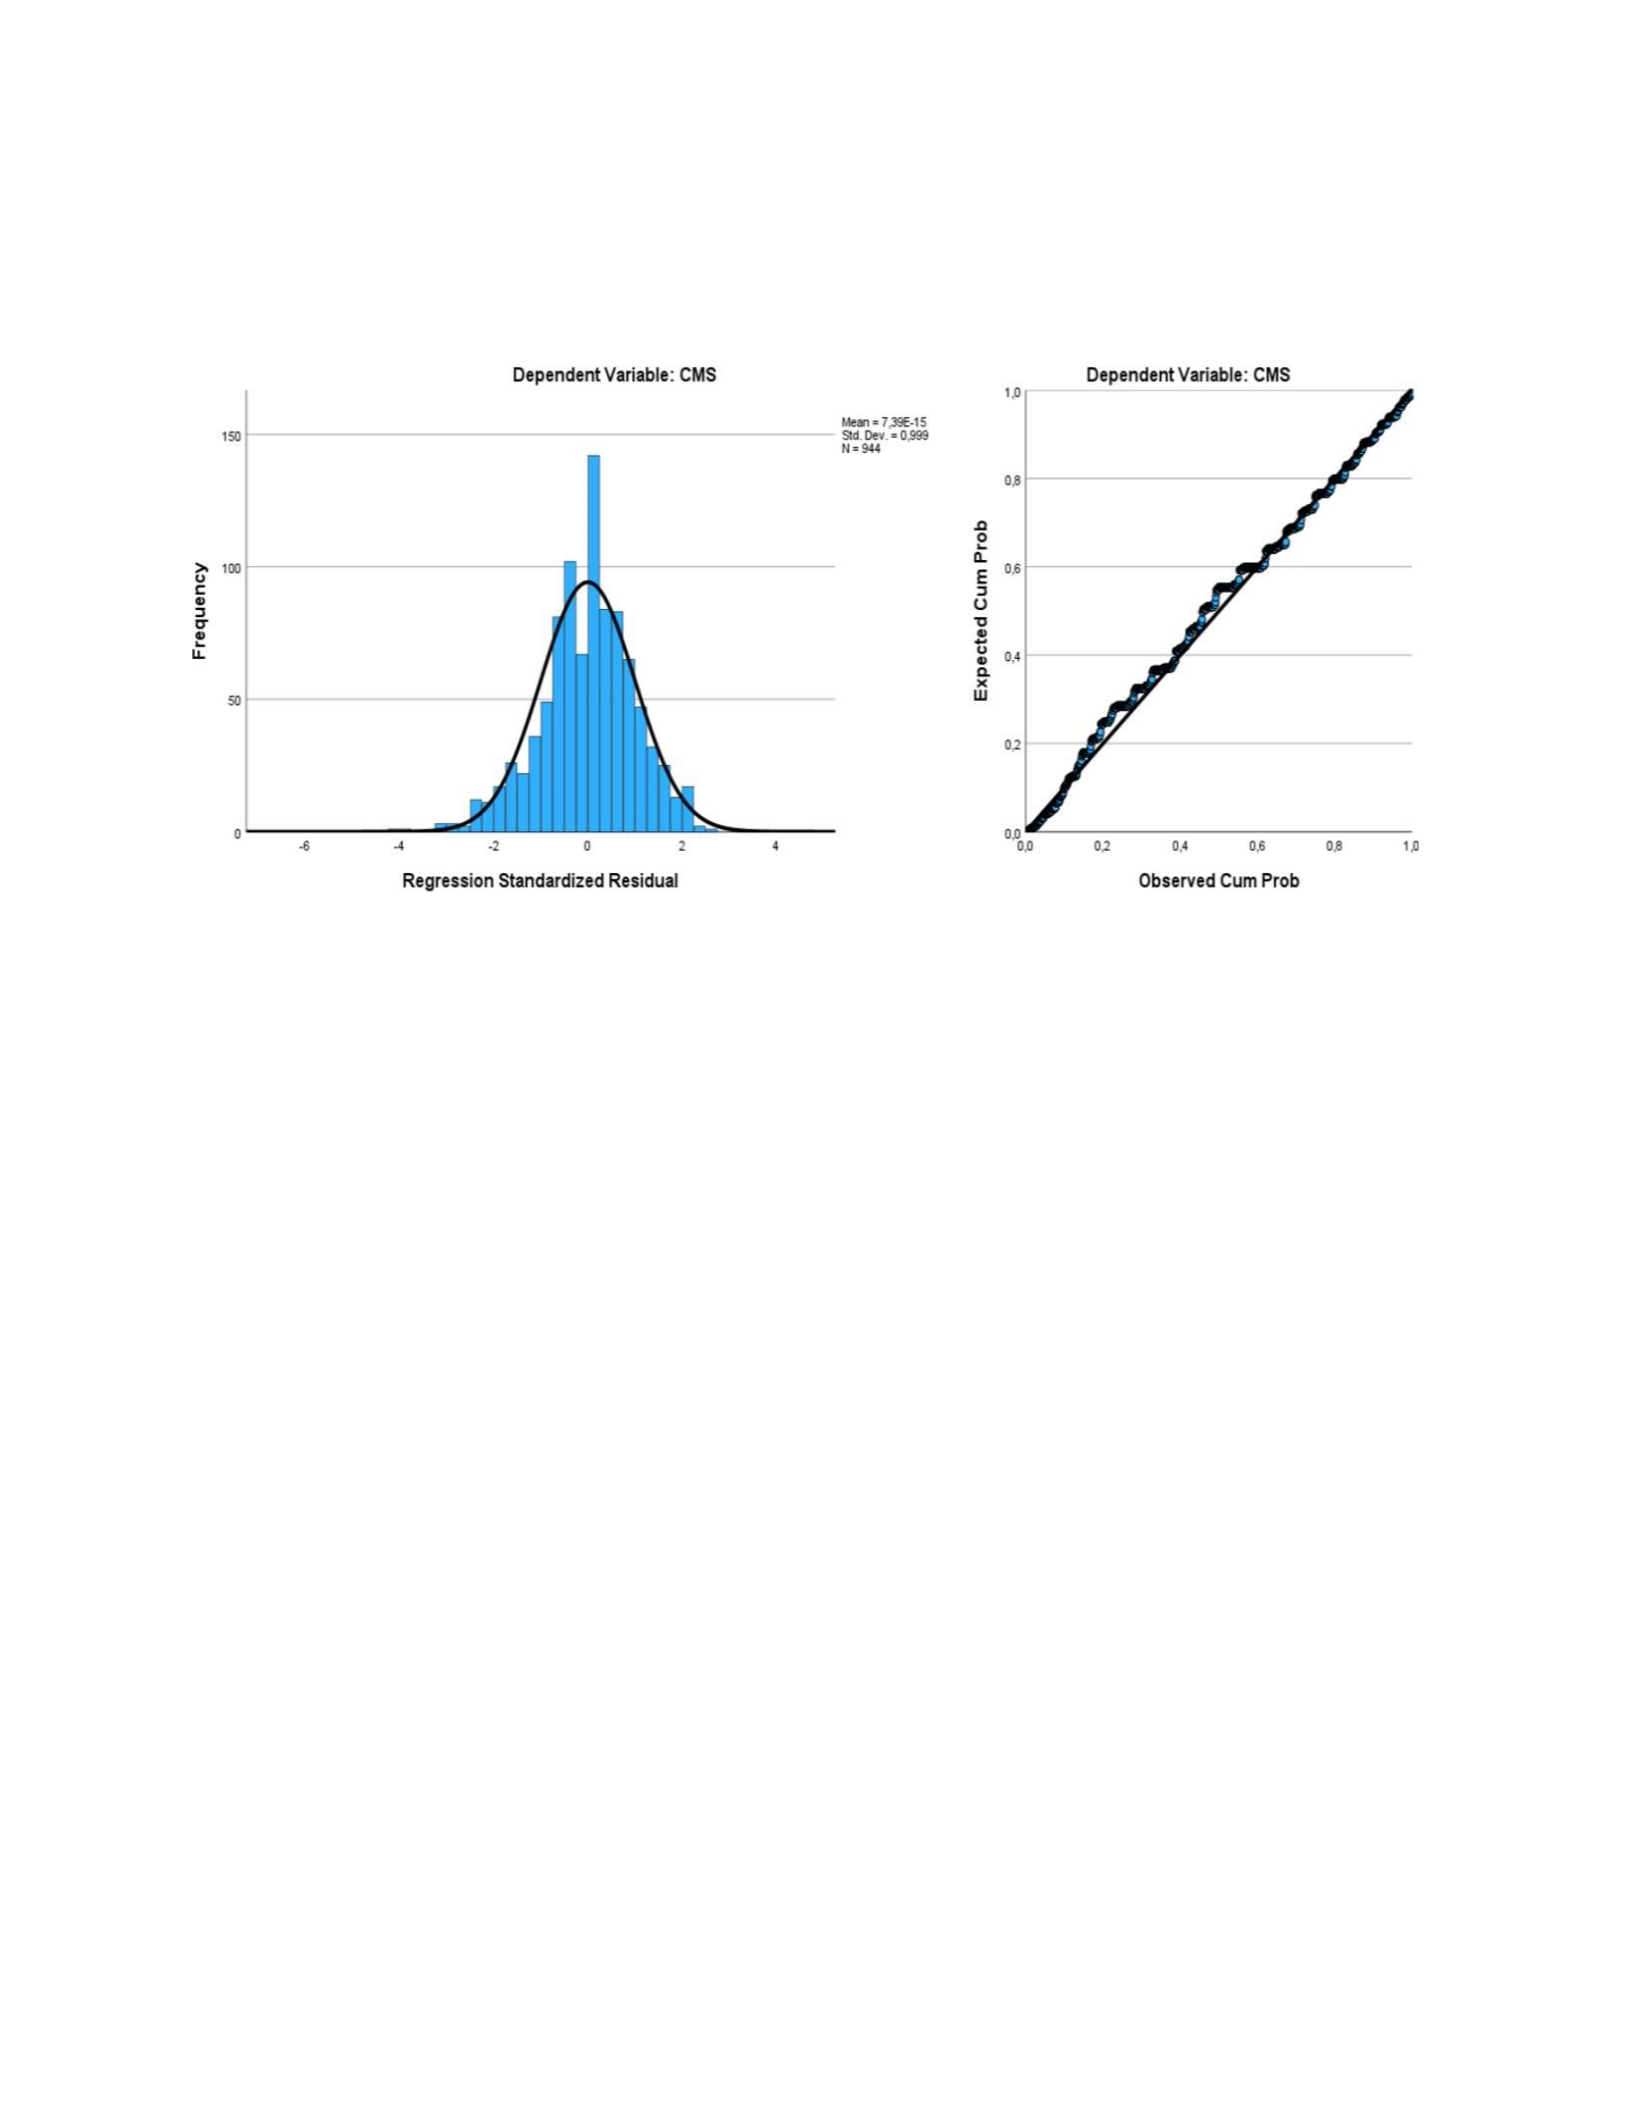
Figure 5
Histogram of the Standardized Residuals and Normal P-P Plot
Note. N = 944, M = 0, and SD = 1.
A simple linear regression was run to understand the predictive ability of psychological
safety on conflict management success. The predictive model was statistically significant, F(1,
942) = 175.44, p < .001, r2 = 0.40. Approximately 40% of the variance in conflict management
success is explainable by psychological safety. Psychological safety was statistically
significantly predictive of conflict management success, B = 0.56, t(942) = 13.25, p < .001,
indicating that for every one unit increase in psychological safety, there was a .56 unit increase in
conflict management success (95% CI, 0.48 to 0.64). Table 10 summarizes the regression model
tested for RQ2.

Table 10
Predicting Conflict Management Success by Psychological Safety
Model
B
SE
95% CI
t
p
LL
UL
(Intercept)
1.64
0.14
1.37
1.92
11.82
<.001
TLPS
.56
.04
.48
.64
13.25
<.001
Note. CI = confidence interval; LL = lower limit; UL = upper limit.
Secondary Analyses: Controlling for Gender and Ethnicity
Secondary analyses were conducted evaluating the effect of gender and ethnicity in
determining if the two variables had a statistically significant difference in the scores for
perceived psychological safety based on the interpersonal conflict management style among NPs
working in interprofessional acute care or critical care teams in the United States. There were a
few challenges with some gender and ethnicity groups having too few participants, which limits
the statistical power to make meaningful comparisons (Shapiro et al., 2021). To address this
issue, certain categories collapsed, combining participants from different gender and ethnic
groups. The following gender categories were grouped: (a) "Gender variant/nonconforming," (b)
"Not Listed," (c) "Prefer not to answer," (d) "Transgender female," and (e) "Transgender male."
The following ethnic categories were grouped: (a) "Multiracial, non-Hispanic," (b) "Prefer not to
answer," and (c) "Some other race alone, non-Hispanic."
Collapsing and combining groups has limitations and disadvantages, as it assumes that
the combined groups share particular characteristics or experiences, potentially introducing
biases and overlooking essential differences between the categories. Furthermore, it may
perpetuate stereotypes and assumptions about certain groups (Shapiro et al., 2021). Despite these

limitations, an ANCOVA was conducted to examine the findings further while controlling for
gender and ethnicity.
The results of the between-subjects effects showed that the corrected model was
statistically significant, F(12, 836) = 11.73, p < .001, partial η^2 = .14. Of primary interest, the
integrating conflict management style had a statistically significant effect on psychological
safety, F(4, 836) = 29.35, p < .001, partial η^2 = .84. Estimated marginal means revealed that the
integrating style had the highest mean (M = 3.44, SE = 0.05, 95% CI [3.34, 3.55]), followed by
compromising style (M = 3.07, SE = 0.06, 95% CI [2.96, 3.18]), dominating style (M = 3.07, SE
= 0.06, 95% CI [2.95 3.19]), avoiding style (M = 3.04, SE = 0.07, 95% CI [2.91, 3.17]), and
finally, the obliging style (M = 2.98, SE = 0.06, 95% CI [2.85, 3.10]).
Gender did not significantly affect psychological safety, F(2, 836) = 0.30, p = .74, partial
η^2 = .001. Although ethnicity did show a statistically significant effect F(6, 836) = 2.49, p =
.021, partial η^2 = .018, post hoc tests did not reveal statistically significant differences between
the ethnicity groups. Given that the findings from the one-way ANOVA without controlling for
gender and ethnicity were consistent with the results from the ANCOVA, the influence of these
demographic variables on the relationship between conflict management styles and
psychological safety appears negligible. Therefore, the results from the one-way ANOVA are
reported in light of these limitations and the observed consistency in findings.
Summary
This chapter presented the results of this quantitative, cross-sectional correlational study.
Overall, it was found that survey respondents reported statistically significant differences in
scores for perceived psychological safety based on their interpersonal conflict management style.
Additionally, psychological safety was found to be a significant predictor of conflict

management success. However, a secondary analysis failed to demonstrate statistically
significant differences in scores for perceived psychological safety based on the interpersonal
conflict management style when controlling ethnicity and gender. Chapter 5 will discuss the
study's results in the context of existing literature and discuss the study's limitations and
proposed research and practice recommendations.

Chapter 5: Discussion, Recommendations, and Conclusion
In the United States, nurse practitioners (NPs) play a pivotal role as members of
interprofessional acute and critical care teams. However, their addition to these teams has led to
an increase in interpersonal conflict between team members (Aberese-Ako et al., 2015; Avgar &
Neuman, 2015; Del Pino-Jones et al., 2019; Donald et al., 2015; Ervin et al., 2018; Glymph et
al., 2015; Kim et al., 2017; Rowland, 2017; Stadick, 2020). To further complicate matters, NPs
receive variable degrees of training in conflict management during their professional education
and enter the workforce with differing degrees of communication and interpersonal problem-
solving skills, which can impact their ability to navigate and manage interpersonal conflict
(Cochran et al., 2018; Field et al., 2014; Moeller & Kwantes, 2015; Samuel et al., 2015).
Psychological safety is an environmental factor that influences how individuals manage
conflict. Individuals who perceive their environment to be psychologically safe are well placed
to identify problems and communication concerns and engage in opportunities for improvement
without fear of retaliation (Burris et al., 2009; Edmondson, 1999, 2019; Edmondson & Lei,
2014; Nembhard & Edmondson, 2006). While psychological safety has been examined in team
settings, until now, there has been limited research examining the interplay between
psychological safety, interpersonal conflict management, and conflict management success,
particularly among NPs who are members of an interprofessional acute or critical care team.
Therefore, the purpose of this cross-sectional, correlational study was to determine if there were
differences in perceived psychological safety associated with interpersonal conflict management
style and to theorize how perceived psychological safety predicts perceived conflict management
success among nurse practitioners working in an interprofessional acute or critical care team in
the United States.

Overall, the results of this study demonstrated that perceived psychological safety
differed significantly based on an NP's interpersonal conflict management style, and
psychological safety was a significant predictor of conflict management success. These
differences were particularly notable for NPs with an integrating conflict management style
compared to other styles (e.g., avoiding, compromising, dominating, and obliging). However,
when controlling gender and ethnicity, there were no statistically significant differences in scores
for perceived psychological safety based on the interpersonal conflict management style. This
chapter includes an in-depth discussion of the study findings, including study implications,
limitations, and recommendations for further practices and research.
Discussion of Findings
Two research questions guided this study: (1) How do scores for perceived psychological
safety differ based on interpersonal conflict management style among NPs working in
interprofessional acute care or critical care teams in the United States? and (2) How does
psychological safety predict conflict management success among NPs working in
interprofessional acute care or critical care teams in the United States? I hypothesized that NPs
who use an integrating conflict management style would have statistically significant differences
in scores for perceived psychological safety. In other words, NPs who report utilizing an
integrating or collaborating style of conflict management would report higher levels of perceived
psychological safety than NPs who use other conflict management styles (e.g., avoiding,
compromising, dominating, and obliging). I hypothesized that psychological safety would be a
statistically significant predictor of perceived conflict management success for the second
research question. Specifically, I expected that higher levels of psychological safety would
predict higher levels of perceived conflict management success. Both hypotheses were

confirmed. Survey results indicated that NPs who use an integrating style of conflict
management perceived higher levels of psychological safety within the interprofessional care
team than NPs who reported other conflict management styles (e.g., avoiding, compromising,
dominating, and obliging). Results also demonstrated that psychological safety significantly
predicts conflict management success. Specifically, psychological safety explained 40% of the
variance in conflict management success.
I expected that NPs with an integrative style of conflict management would perceive
higher levels of psychological safety compared to NPs who use one of the other four styles of
conflict management because an integrating style of conflict management inherently involves
open communication, mutual respect, and a shared sense of responsibility, which are crucial
elements for a psychologically safe environment.
In a collaborative setting, NPs are encouraged to voice their opinions, raise concerns, and
suggest improvements without fear of backlash or retribution. When team members actively
collaborate, trust is established and reinforced. Conversely, other conflict management styles like
avoiding or dominating often halt open communication and create an atmosphere of mistrust. In
such environments, individuals are more likely to exhibit a lower level of concern for themselves
and others, and as a result, conflict is less likely to be managed collaboratively and addressed
openly (Fleming & Shaw, 2019; Hocker & Wilmot, 2018; Rahim, 1983; Thomas & Kilmann,
1974).
I also expected that higher levels of psychological safety would predict higher levels of
perceived conflict management success. This expectation was partly based on Edmondson's
(1999, 2019) research on psychological safety and Tekleab et al.'s (2009) research on conflict
management success. These studies agree that individuals operating in a psychologically safe

environment tend to demonstrate concern for themselves and others and facilitate effective
communication. The respect that is shared between members and the open communication, in
turn, creates a generative ground for effective conflict management. When team members feel
empowered to voice their concerns, offer constructive criticism, and engage in collaborative
problem-solving, the likelihood of successful conflict management increases. It is worth noting
that the environmental setting is critical when investigating the interplay between psychological
safety, conflict management style, and conflict management success (Fleming & Shaw, 2019;
Hocker & Wilmot, 2018; Rahim, 1983; Thomas & Kilmann, 1974).
Bandura's (1977, 1986) SLT provides a framework for interpreting the results of this
study. According to Bandura (1977, 1986), individuals learn through dynamic and static means
by observing and interacting with others in their environment. Through this process, a reciprocal
triadic relationship emerges between one's environment (interprofessional healthcare team and
psychological safety), behavior (conflict management style), and cognition (psychological safety
and conflict management success). In other words, one's environment facilitates psychological
safety, building conflict management self-efficacy and leading to success. Likewise, the degree
of one's psychological safety is also likely to influence their environment reciprocally.
While not directly studied in this research study, self-efficacy is the cornerstone of SLT.
Self-efficacy is an individual's belief in their ability to carry out behaviors necessary to produce
specific outcomes (e.g., functioning as a part of a team or managing conflict successfully). It is
developed through mastering experiences, social modeling, persuasion, and appropriate
psychological responses (Bandura, 1977, 1986, 1994). Self-efficacy and an integrating conflict
management style are associated with effective problem-solving, collaboration, and cooperation
(Bandura, 1977, 1986; Rahim et al., 2000). For example, for NPs to manage conflict

successfully, they must be willing to take risks, challenge the status quo, and advocate for
themselves. An individual will likely not be willing to take risks, challenge the status quo, or
advocate for themselves and others if the environment is not psychologically safe. The current
study's findings underscore the potential significance of individuals with a strong sense of self-
efficacy, as they tend to embrace challenging tasks, take calculated risks based on their strengths,
and maintain confidence in their abilities (Bandura, 1994), and warrants further research.
Individual, team, and organizational contextual factors (e.g., hierarchy, culture,
organizational support, and individual members' confidence levels) influence psychological
safety (Edmondson, 2019; Grailey et al., 2021). For example, environments with a flat hierarchy,
with little to no power dynamics between team members, promote psychological safety (Cullati
et al., 2019). However, there are often power differences between physicians and other
healthcare professionals in an acute or critical care setting. These power dynamics threaten
professional identities and often lead to decreased trust, respect, teamwork, and collaboration
(Kim et al., 2017; Mitchell et al., 2019). To further complicate matters, individuals may adapt
their conflict management style based on the context of the conflict (Callanan et al., 2006). In
other words, an NP may utilize an integrating style of conflict management in a setting where
they feel psychologically safe and supported but may resort to another style, such as avoiding or
compromising in environments where power differentials and hierarchical structures are more
pronounced. This adaptative approach to conflict management reflects the complexity of
interprofessional relationships in healthcare, where various contextual factors deeply influence
individual behavior and warrants additional investigation in future studies by examining the
interplay between psychological safety and conflict management style through either mixed-
methods or qualitative approaches.

Findings indicate that psychological safety explained 40% of the variance in conflict
management success. This indicates that being respected, accepted, and able to speak openly
without fear of judgment or retribution significantly influences the success of conflict
management within interprofessional acute and critical care teams. Furthermore, this study
demonstrates that a psychologically safe environment fosters better collaboration and
communication, leading to successful conflict management. This finding is essential in acute and
critical care settings, where decisions must be made quickly due to rapidly changing conditions.
There is less time for deliberate reflection or extensive conversations in these settings, and teams
must function cohesively to adapt to swiftly changing circumstances. As such, there is a higher
likelihood of increased conflict in acute and critical care settings, which can potentially impact
patient outcomes as well as patient, individual, team, and organizational satisfaction (Alexanian
et al., 2015; Andreatta, 2010; Ervin et al., 2018; Hughes et al., 2016). Therefore, additional
research is warranted to examine the interplay between psychological safety and conflict
management of NPs working in an inpatient, interprofessional environment.
These findings have several notable implications. First, the findings suggest that
psychological safety is integral to the functioning of acute and critical care teams, where rapid
decision-making and team cohesion are critical. Notably, NPs with an integrating conflict
management style perceived higher levels of psychological safety than their peers who used
other conflict management styles. This finding highlights the potential interplay between the
psychological climate within a team and different conflict management approaches. Likewise,
this finding also points to the critical role of a psychologically safe environment in shaping
interactions and outcomes among interprofessional team members to achieve appropriate patient
outcomes and improve professional and patient satisfaction. Furthermore, this style reveals that

psychological safety accounts for nearly half of the variance in conflict management success,
underscoring its importance as a substantial factor in team dynamics.
How Findings Align With Past Literature
The findings of this study align closely with several aspects of existing literature on
psychological safety and conflict management. Research has shown that a psychologically safe
environment can mitigate the interpersonal risks inherent in teams, particularly traditional
hierarchical teams, such as interprofessional healthcare teams (Grailey et al., 2021; Kim et al.,
2017). Moreover, although not within a healthcare context, Joo et al.'s (2023) study found that
organizational trust and empowered leadership explained a substantial variance in employee
psychological safety and conflict management success. This further reinforces the notion that a
psychologically safe environment can influence conflict management, as supported by the
current study, where psychological safety explained 40% of the variance in conflict management
success.
Similarly, published research by Edmondson et al. (2001), Grailey et al. (2021), and
Kilcullen et al. (2022) highlighted the importance of psychological safety in fostering open
dialogue and constructive feedback, which is essential for team learning and cohesion. Their
findings align with my research, which identified the connection between high levels of
perceived psychological safety and integrating conflict management styles, thereby highlighting
psychological safety's vital role in facilitating effective collaboration and collaborative problem-
solving within interprofessional healthcare teams. Erkutlu and Chafra (2015) found that
cooperative conflict management mediates psychological safety and employee voice, further
emphasizing its impact on creating an environment where individuals feel safe expressing their
ideas and opinions.

How Findings Conflict With Past Literature
This study's findings partly diverge from existing literature. In order to understand the
divergence, it is essential to note that the literature on conflict management styles among nurses
primarily focuses on staff nurses and nurse managers (Al Hamdan et al., 2011, 2014; Ardalan et
al., 2017; Ebrahim et al., 2014; Hendel et al., 2005, 2007; Tabak & Orit, 2007), presenting
challenges comparing findings across the studies. One notable difference between my study and
prior studies is that an integrative style of conflict management was reported at a higher
frequency in NPs working in the acute and critical care setting compared to other styles (e.g.,
avoiding, compromising, dominating, and obliging), which is not reflected at all in the literature.
Labrague et al.'s (2018) study reported that most nurses used a dominant conflict management
style. Research from various countries reveals that nurse managers in Oman and Jordan are
likelier to employ a dominating style than those in the Philippines and India (Al Hamdan, 2009;
Al Hamdan et al., 2011, 2014, 2016). Further complexity is added by contextual factors, with
Callanan et al. (2006) noting that individuals adapt their styles based on the conflict context and
Edmondson et al. (2001) highlighting the role of culture and context, particularly in settings with
a hierarchical culture.
For instance, individuals in lower hierarchical positions, like nurses and support staff,
may be hesitant to voice their opinions due to potential censure from those in higher positions,
such as physicians. Varying contextual factors make it challenging to compare this study's
findings in acute and critical care settings to existing literature.
Psychological safety is predicated on the constructs of conflict management and the
overall culture among the parties involved. Cultures and environments that demonstrate respect
for individuals create value and facilitate effective communication and a sense of security

(psychological safety), which enables effective conflict management and leads to conflict
management success (Edmondson, 2019; Ervin et al., 2018; Kilcullen et al., 2022; Tekleab et al.,
2009). However, what is not fully understood is the role gender and ethnicity have in the
interplay of psychological safety and conflict management. The extant literature includes mixed
findings regarding gender, ethnicity, and perceived psychological safety.
Most research on psychological safety has been conducted in Western cultures, where
individuals are more likely to voice their concerns and ideas, than in Eastern cultures, where
power differences and uncertainty avoidance are more pronounced (Newman et al., 2017). While
the impact of psychological safety in Eastern cultures is not entirely understood, it is reasonable
to expect that psychological safety would have different outcomes, especially in settings where
speaking out, providing feedback, and endorsing new ideas is less supported. In situations such
as these, the potential cost is much greater than in Western cultures, especially as individuals risk
losing face and being ostracized by others as these behaviors are considered to be impolite
(Edmondson & Lei, 2014; Friedman et al., 2006; Liu et al., 2014).
From the perspective of gender, the findings of the extant literature are mixed as well.
Historically, males are more likely to engage in risky behavior than females, suggesting that a
difference may exist between genders in risk-taking and psychological safety (Fisk, 2018). The
premise is that psychologically safe individuals are more willing to engage in perceived or risky
behaviors. However, a study by Holley and Steiner (2005) found no differences between gender
and feeling safe (i.e., psychological safety) in an academic setting, nor did a study by Nembhard
and Edmondson (2006) that examined different members of an interprofessional healthcare team
and the impact of psychological safety. In their study, Nembhard and Edmondson (2006) found
gender not predictive of the degree of psychological safety in the ICU. These findings are similar

to my study when controlling for gender and ethnicity. I found no statistically significant
differences in scores for perceived psychological safety based on the interpersonal conflict
management style.
Limitations
Several potential limitations emerged during the study and are related to the study design,
data collection, data analysis, and study results. Limitations of cross-sectional survey designs
include response, sampling, selection bias, generalizability, and scope. The sample for this study
included NPs working in acute or critical care settings in the United States or its territories. Thus,
the findings of this study may not be generalizable to other healthcare settings, such as NPs
working in other areas such as primary care, psychiatric /mental health, pediatrics, or women's
health. The acute and critical care environment is highly temporal, and the patients tend to be
seriously ill or injured with little room for error (Ervin et al., 2018; O'Donovan & McAuliffe,
2020) Further, the sample may not be representative of all NPs, particularly those in other
countries with different healthcare systems or cultural contexts. In addition, it is impossible to
know if the characteristics of the sample are different from nonresponders, which may have
resulted in selection bias. A third limitation of the study design is related to self-report and
response bias. The study participants may have provided socially desirable responses or could
not accurately recall all of their experiences managing conflict as part of an interprofessional
healthcare team.
Although the study used well-validated instruments, there is no guarantee that the
participants understood the questions. In addition to the inherent nature of surveys, participants
often feel limited by the range of responses (Delva et al., 2002). Given the temporal nature of
surveys, this study was designed with a limited number of questions to avoid fatigue.

Furthermore, participants were provided with a personal link and could return to the survey as
their schedule allowed. The recruitment window was kept open for the entire study, allowing the
participants ample time to complete the survey.
It is also important to note that some of the completed surveys appear to be answered by
automated software or were bot responses, which is a limitation of online research. These
limitations were mitigated by completing a line-item analysis of the responses to identify and
remove cases with zero response variation. In addition, despite extreme care, I made an error
when building the survey in Qualtrics. Edmondson's (1999) Psychological Safety Subscale and
Tekleab et al.'s (2009) Conflict Management Success Subscales were inadvertently built with a
5-point Likert scale instead of the 7-point Likert scale used by the authors. Given the change in
response options, assessing whether the adapted survey scales still measured the same constructs
as the original scales is crucial. Therefore, confirmatory factor analyses were conducted to
confirm that the factor structure of the adapted scales is consistent with the original scales and to
examine the scales' validity in measuring the constructs of interest. The results of the analyses
confirmed that both subscales maintained the same factor structure as the original scale.
Additionally, Cronbach's alpha coefficients observed for both scales indicated internal
consistency and reliability. The confirmatory factor analyses, and Cronbach's alpha findings
suggest that these adapted scales are valid and reliable measures of both original scales and can
be used confidently.
Implications and Recommendations for Future Research
The findings of this study yield valuable insights into the interplay between perceived
psychological safety, conflict management styles, and conflict management success among NPs
working in interprofessional acute or critical care teams. Future researchers might consider

expanding the geographical scope of the research to enhance generalizability, as this study was
confirmed to NPs working in acute and critical care settings in the United States. Future research
could include NPs from other countries to account for differences in healthcare systems and
cultural variations (Hofstede, 2001). A longitudinal design, as opposed to the cross-sectional
approach used for the current study, may offer a more comprehensive and nuanced
understanding of how psychological safety and conflict management evolve, particularly in high-
stakes, rapidly changing environments like acute and critical care settings. In addition, the
absence of a universally accepted instrument for measuring psychological safety and conflict
management styles in healthcare settings suggests the need for validated instruments specific to
healthcare professionals (Grailey et al., 2021; Hunt et al., 2021).
Further research into the potential significance of the mixed styles category identified but
subsequently excluded in my study is warranted. The mixed styles emerge from the ROCI-II
questions and are based on the Dual Concerns Model (DCM). Rahim (1983) did not explicitly
address mixed styles of conflict management and theorizes that individuals will identify with a
primary conflict management style. However, his research is over forty years old, and attempts
have yet to be made to update the categories of conflict management styles. Given the changes in
society and individual, team, and group dynamics, it is time to reevaluate the different styles of
conflict management to better understand the impact of conflict management styles.
Although the adapted scales in this study showed internal consistency, further research
should consider the consequences of adapting scales, especially when varying from the original
Likert scale points. Replication studies could aim to use the original 7-point Likert scales as
utilized by Edmondson (1999) and Tekleab et al. (2009) and compare results to assess the impact
of this methodological alteration. Moreover, it may be beneficial to control for variables such as

age, gender, years of experience (both in total and in the same practice setting), and facility type,
which have been observed to include conflict management styles (Akel & Elazeem, 2015; Al
Hamdan et al., 2011, 2014).
More robust mechanisms to control for response and selection bias could be employed.
Triangulating self-reported data with other sources, such as peer review or supervisor
assessments, could mitigate issues of socially desirable responses and recall affecting self-report
data (Delva et al., 2002). Given the limitations reported to both responses, rigorous validation
and verification steps during data collection are advisable.
The findings of this study demonstrated statistically significant differences in levels of
perceived psychological safety based on an individual's conflict management style. However, the
extent to which psychological safety influences responses to various conflict management
strategies – particularly over different timeframes and situational contexts – remains unclear.
One challenge to understanding this interplay is that Rahim's (1983) seminal work and this study
are based on the DCM. The DCM provides valuable insights into how individuals and
organizations handle conflict but does not explicitly address whether or not an individual's
conflict management style changes over time. Furthermore, while Rahim's (1983) work offers a
framework for understanding and categorizing different conflict management styles, he does not
make explicit claims about their malleability or suitability over time. However, it is widely
accepted that conflict management style, similar to emotional intelligence, is not static; it evolves
based on numerous factors, including personal and professional experiences, situational
variables, and relationship dynamics. However, whether certain conflict management styles
predispose individuals to higher or lower perceptions of psychological safety remains unclear.
Future research should focus on the interplay between psychological safety and conflict

management styles, mainly on how psychological safety influences one's conflict management
style in varied environments. While it is beyond the scope of this study, future research
examining the potential impact of increasing the integrating conflict management style is
warranted.
Additional research could also delve deeper into the role of the environment in
influencing conflict management styles, particularly in acute and critical care settings, as well as
examining the predictors of psychological safety of interprofessional healthcare teams. Finally,
qualitative studies may serve as a valuable complement to quantitative data, shedding light on
the lived experiences of NPs managing conflict in interpersonal care teams. By following these
recommendations, future research can provide a more nuanced and comprehensive
understanding of the complex interplay between psychological safety and conflict management
among NPs and other healthcare providers.
Implications and Recommendations for Practice
Based on the study's findings, the following practice recommendations are offered to
enhance psychological safety and improve conflict management among NPs in interprofessional
healthcare teams. Given the significant correlations between psychological safety and conflict
management success, healthcare organizations may prioritize psychological safety and conflict
management training programs that encourage open communication and constructive feedback.
Regular assessments of psychological safety levels should be conducted, and targeted
interventions to improve the environment should be implemented. Given the differences in
conflict management styles among nurses, as highlighted by Labrague et al. (2018) and
Blackwell and Faraci (2020), there is a need for tailored training programs encompassing various
conflict management approaches. To facilitate this, standardized assessment tools for gauging

psychological safety and conflict management styles, similar to those devised by Edmondson
(1999), Rahim (1983), and Tekleab et al. (2009) should be employed. From an organizational
standpoint, leaders play an irreplaceable role in sustaining a psychologically safe environment.
Interprofessional care team leaders should model appropriate behaviors and adopt a management
style that fosters collective responsibility and accountability (Hunt et al., 2021).
A 'one-size-fits-all' approach is not possible for organizations and leaders to establish a
psychologically safe environment, which should be tailored to the specific needs of individual
teams and broader organizational structures (Hunt et al., 2021). The perception of psychological
safety will likely vary depending on environmental factors and conflict management style.
Therefore, organizational training related to effective conflict management skills should include
key concepts of psychological safety, conflict management styles, and conflict management
success through a dynamic lens, as one's conflict management style will likely change over time.
Additionally, there remains a high likelihood of having different conflict management styles
within the team or organization and varying degrees of perceived psychological safety among
team members. Furthermore, the perceived degree of psychological safety is subject to change
depending on situational and interpersonal relational factors involved. While an integrative
conflict management style is often recognized as the most effective, different styles can be
applied depending on the different stages or types of conflict (Fleming & Shaw, 2019; Hocker &
Wilmot, 2018). Sometimes, depending on environmental and contextual factors, a different
conflict management style is more beneficial.
Leaders should be taught to create an environment that fosters psychological safety and
effective conflict work. Teaching and supporting leaders in developing and deploying
psychological safety is essential, as psychological safety is both an individual and team

construct. One's environment facilitates psychological safety, but psychological safety heavily
depends on leaders and organizations fostering and supporting the team in achieving a
psychologically safe environment. Organizations that disregard the principles of psychological
safety and effective conflict management are at risk of staff attrition and compromised clinical
outcomes, as underlined by recent reports indicating that a significant percentage of nurses are
contemplating changing careers due to burnout and a lack of emotional support (LeClaire et al.,
2022).
Given the cultural diversity often present in healthcare, it is also essential to incorporate
cultural competence (Hofstede, 2001) in conflict management training, as studies by Akel and
Elazeem (2015) and Al Hamdan et al. (2011, 2014) have indicated that culture can influence
conflict management styles. In the high-stakes acute and critical care environment, the
importance of interprofessional collaboration cannot be overstated (Ervin et al., 2018; Grossman
et al., 2021). This involves standardizing protocols and guidelines to foster teamwork and
mechanisms for peer and supervisory review. By integrating these recommendations into
practice, healthcare organizations can foster an environment supporting successful conflict
management and deepening psychological safety, benefiting healthcare providers, organizations,
and their patients.
Conclusion
This study explored the interplay between perceived psychological safety, interpersonal
conflict management style, and conflict management success of NPs working in interprofessional
acute care and critical care teams in the United States. The findings of this study indicate that
NPs in this context most frequently preferred an integrating style, which aligns with their
collaborative and team-oriented nature in complex healthcare settings. The integrative or

collaborative style promotes problem-solving and cooperation, facilitating successful conflict
management within the interprofessional team. As such, the results emphasize the significance of
understanding and assessing individual conflict management styles to promote effective
teamwork and conflict management in acute and critical care settings. Additionally, this study
found that psychological safety is a significant predictor of the perceived conflict management
success of NPs in a complex healthcare team.
The research findings have significant implications for NPs, healthcare organizations, and
team leaders. Recognizing and fostering a psychologically safe environment is crucial for
promoting effective conflict management and teamwork among NPs. Healthcare organizations
should prioritize creating a supportive and collaborative culture where NPs feel safe to express
their opinions, voice concerns, and actively participate in conflict management without fear of
negative consequences. Leaders need to model appropriate behaviors and endorse practices that
support psychological safety and open communication within the team. Additionally, the study
highlights the need for conflict management training tailored to NPs' needs. By equipping NPs
with effective conflict management skills and promoting psychological safety, healthcare
organizations may enhance team dynamics, improve patient outcomes, and create a more
supportive and fulfilling work environment for NPs. Bandura's (1977, 1986) SLT provided a
framework for understanding the results of this study, which demonstrated that conflict
management success is achieved based on an individual triadic relationship between one's
environment, behavior, and cognition and working in a psychologically safe environment.
Despite its contributions, this study has some limitations that should be acknowledged.
The use of self-report surveys may be subject to social desirability bias and response errors,
potentially affecting the accuracy of the data collected. Additionally, the sample was limited to

NPs working in interprofessional acute and critical care teams in the United States, which may
limit the generalizability of the findings to other healthcare settings or countries with different
cultural contexts. Future research should consider using qualitative or mixed method approaches
and exploring conflict management styles in diverse healthcare contexts to provide a more
comprehensive understanding. Furthermore, developing validated instruments specific to
healthcare professionals for measuring psychological safety and conflict management styles
would enhance the accuracy and reliability of future studies in this field. Overall, this study is a
valuable contribution to the growing body of knowledge on conflict management in healthcare
and lays the groundwork for future research and interventions to promote effective teamwork
and collaboration among nurse practitioners.

