


1
Chapter 1: Introduction
We have an incarceration rate in the United States - the world's greatest democracy
- that is five times as high as the incarceration rate of the rest of the world. There's
only two possibilities here ... Either we have the most evil people on earth living in the
United States or we are doing something dramatically wrong in terms of how we
approach the issue of criminal justice. Former US Senator Jim Webb (Webb, 2009)
Since their inception in the late 1980’s, drug courts have become a fixture of criminal
justice throughout the United States. There are currently 2,968 Drug Courts in operation in every
US state and territory (“How Many Drug Courts”, 2016). The first drug court was established in
Dade County, Florida in 1989 (Belenko, 1999). The original drug courts were an effort to deal
with a “revolving door” justice system where the same offenders cycled in and out of courts and
prison (Huddleston, Freeman-Wilson, Marlowe, & Roussell, 2005). The courts offered a way to
deal with the root cause of low-level drug offenses by addressing addiction, seen as the primary
problem of these offenders.
The genesis of drug courts was just the latest attempt to find a balance between punitive
measures and recognition of drug abuse as a social and physical problem in need of treatment as
well as punishment. The first major national narcotics law, the Harrison Act of 1914, was
intended to curb recreational drug use and nonmedical addiction (Musto, 1973). Since that time,
there have been numerous initiatives aimed at coming to terms with drug use in American
society. These attempts have ranged from “tough on crime” efforts such as the “Three Strikes
and You’re Out” initiative in California during the nineties to a current major initiative of some
states legalizing marijuana. Drug courts emerged during the worst years of the 1980’s crack
epidemic and, despite the emergence of new challenges remain as relevant today as they were
thirty years ago.

2
There is a historical context for the emergence of drug courts as a specialized justice
system intended to address a particular population of concern and a set of social problems. In
1899, the Chicago Juvenile Court was concentrated on “petty offenses and salvageable offender”
(Fox, 1970). Prior to this time, juveniles were tried and judged in the adult justice system (the
only one that existed up to that point). It can be argued that drug courts have grown from those
earliest efforts at courts acting not only as a means of punishment but also as a means of
addressing a particular population. It can further be argued that, over time, these courts are an
effort to address a social problem and the root causes of crime. While not unprecedented in the
effort to ‘reform’, drug courts are a unique innovation very much designed to address a modern
social problem.
This chapter will lay the groundwork for this study by providing a definition of drug
courts and their basic tenets. The remainder of the chapter will provide a problem statement
outlining the current context and environment in which drug courts operate, discuss the
significance of drug courts in the field of social work and describe a brief study overview.
Defining Drug Courts
Drug courts were born of necessity after the growth of drug related arrests threatened to
overwhelm the criminal-justice system in the early 1980’s (Belenko, 1999). The emergence of
crack cocaine was a particularly onerous problem driving the increase in drug related arrests and
incarcerations. The result of this huge increase in drug crime and arrests was a “revolving door”
system with drug offenders cycling in and out of the system with no apparent progress being
made. Faced with the lack of resources brought about by the crack epidemic, many jurisdictions
began to seek alternatives to the traditional court approach to drug offenses and addiction. The

3
innovative approach these new courts brought to bear was the effort to quickly identify substance
abusing offenders and place them under strict court monitoring and community supervision
(Huddleston, et al., 2005). These courts represented an innovative paradigm shift at the time,
best described as “therapeutic jurisprudence.” To quote the Department of Justice:
The premises of therapeutic justice are that law is a therapeutic agent; positive
therapeutic outcomes are important judicial goals; and the design and operation of the
courts can influence therapeutic outcomes. (Simpson, 2015).
The quotation above represents the sentiment that treatment professionals and law enforcement
officials share the same goal when it comes to persons with substance use disorders—a reduction
in substance abuse and in criminal behavior related to that substance abuse.
Drug courts represent a coordinated effort that brings together the efforts of judiciary,
prosecution, defense bar, probation, law enforcement, treatment, mental health, social services
and child protective services (Huddleston, et al., 2005) to break the cycle of drug addiction,
criminal behavior and substance abuse. This coordinated approach brings together multiple
resources, from multiple agencies, in a way not possible prior to the establishment of drug courts.
In this blending of systems, the drug court participant undergoes an intensive regimen of
substance abuse and mental health treatment, case management, drug testing, and probation
supervision while reporting to regularly scheduled status hearings before a judge (Huddleston, et
al., 2005). Job skills training, family or group counseling, and other life-training skills are
examples of the innovative services a drug court may provide participants (Huddleston, et al.,
2005). This comprehensive approach is a significant change from the “lock them up and throw
away the key” mindset of many mainstream courts. By addressing the problem through a less

4
paternalistic lens and more cognizant of the application of power, drug courts represent a unique,
new and proactive way to deal with low level drug offenders.
According to John Walters, Director of the Office of National Drug Control Policy, “drug
courts are one of the most significant criminal-justice initiatives in the past twenty years”
(Huddleston, et al., 2005). The rapid growth of drug courts supports this sentiment. Drug courts
have proliferated throughout the country at a rapid pace since the establishment of the first one in
1989. Currently, 50 states plus the District of Columbia, Northern Mariana Islands, Puerto Rico,
Guam, two Federal Districts and 121 tribal programs have drug courts that are in operation or are
being planned (“Drug Courts”, 2015).
Statement of the Problem
Addiction and rising incarceration rates are problems that continue to vex American
society and the American justice system. These twin problems directly influence the need for a
policy solution like drug courts.
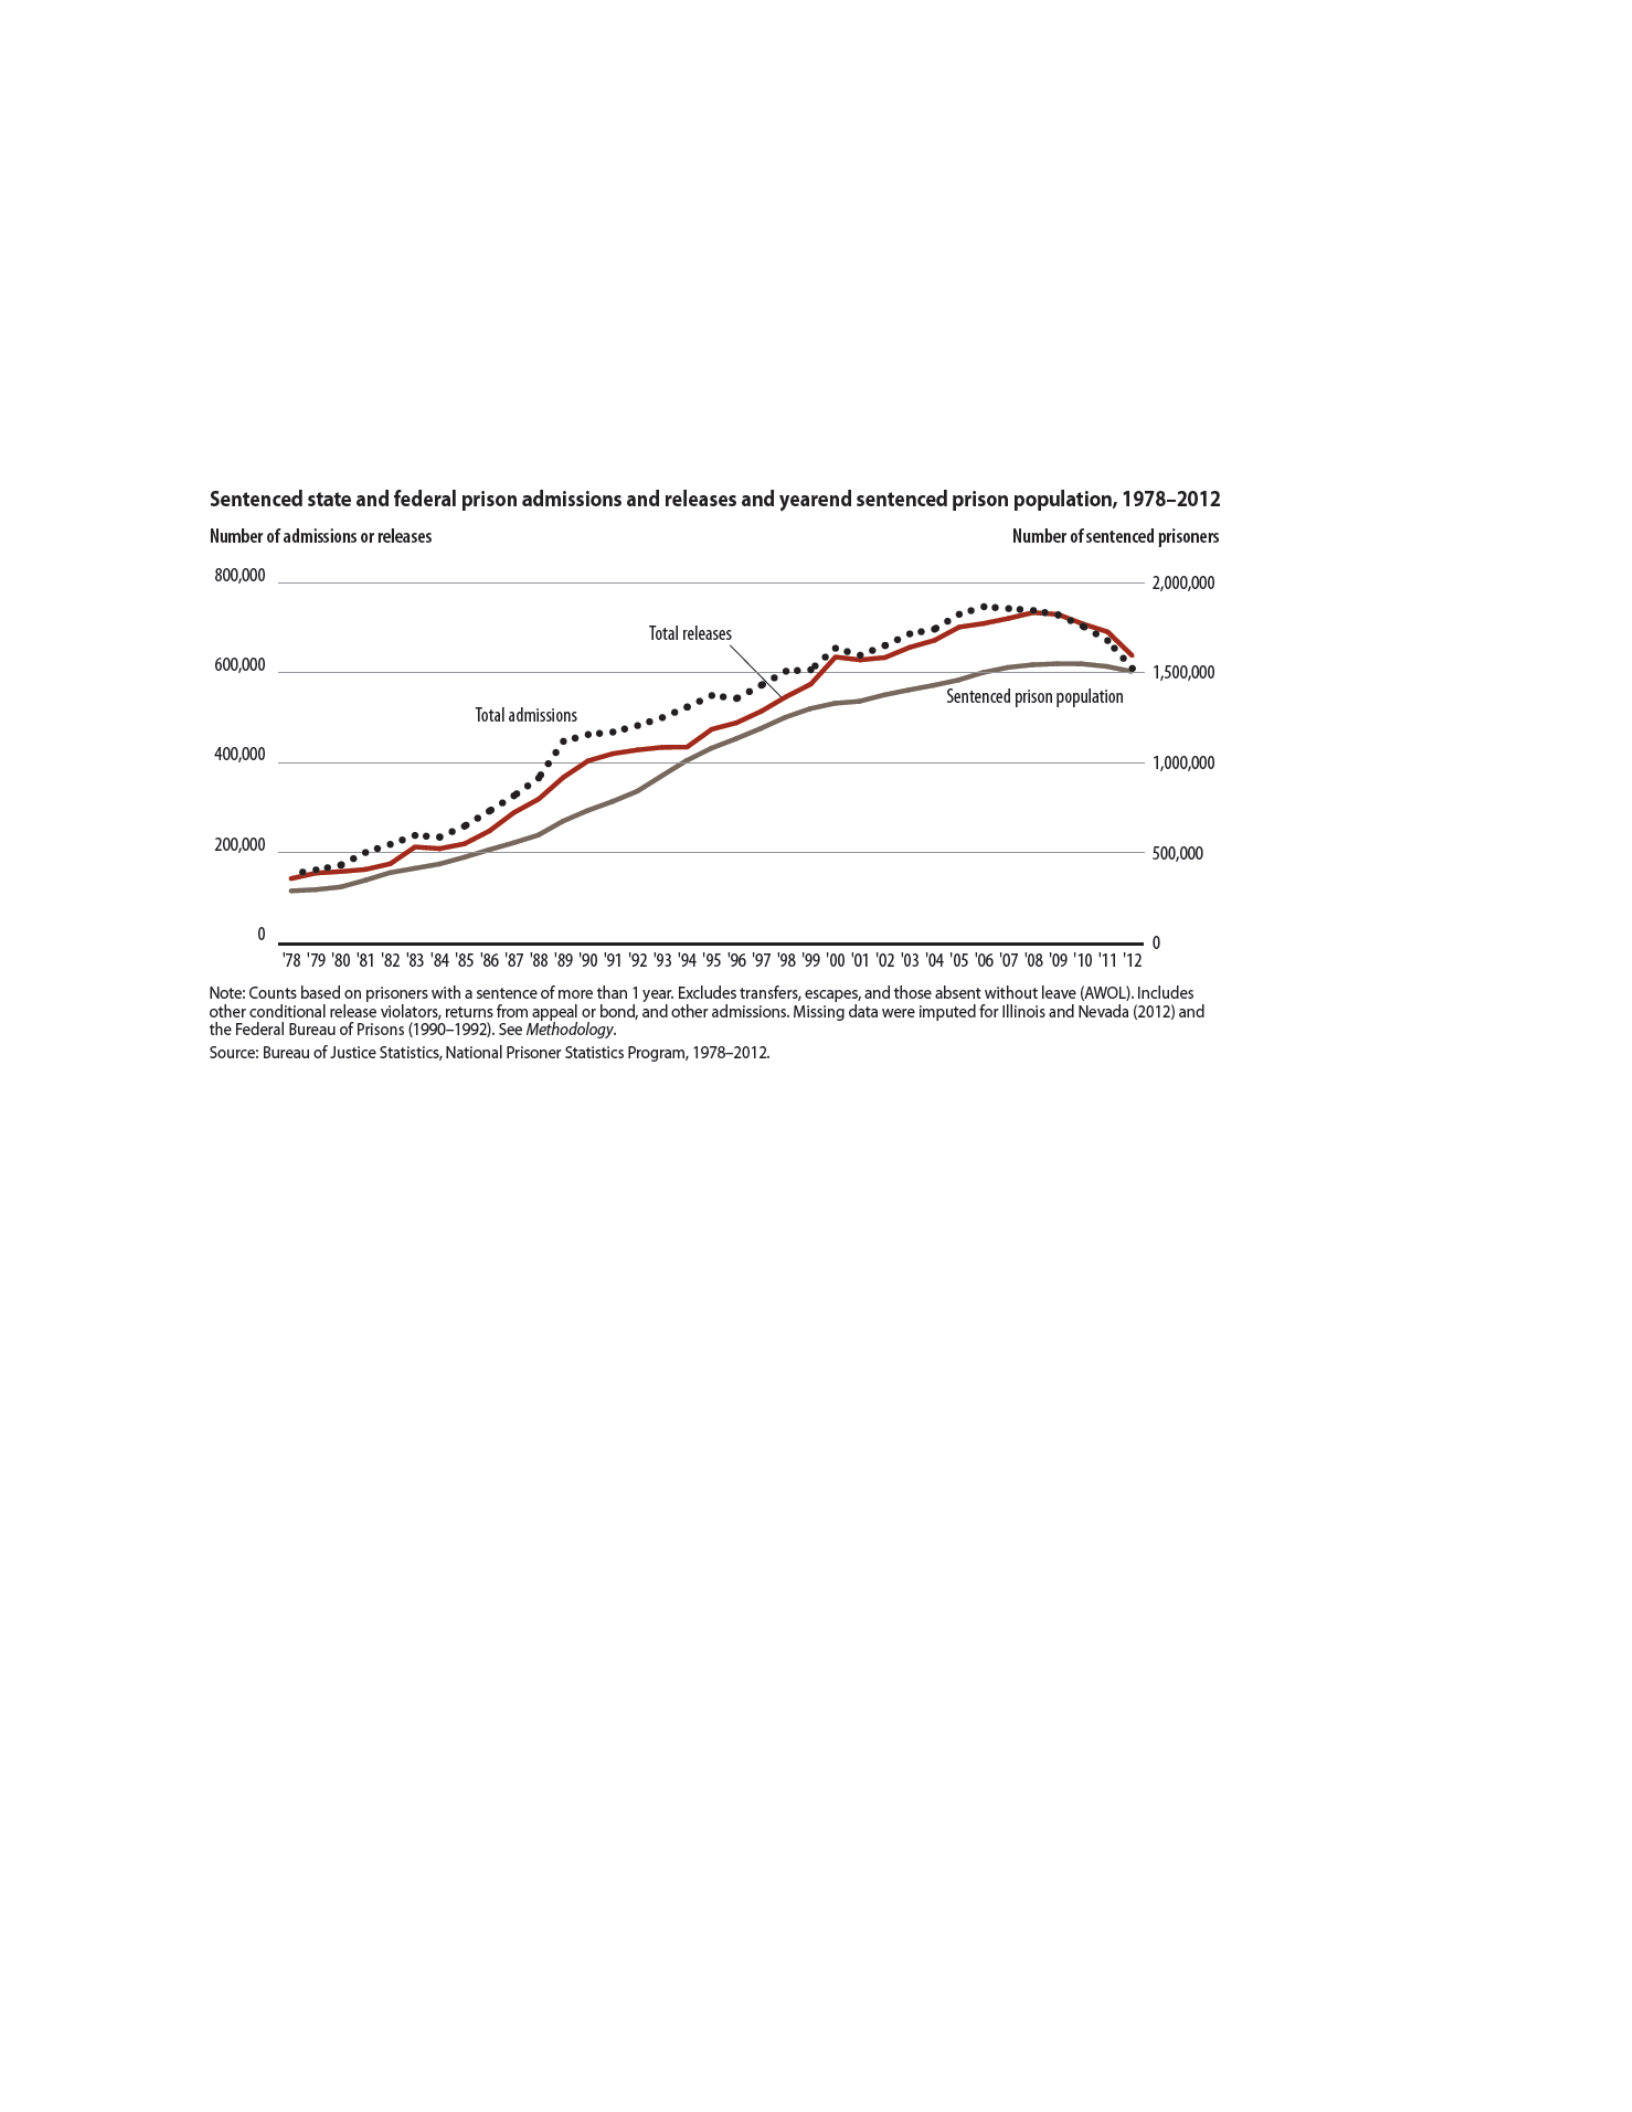
The American prisoner population has skyrocketed over the last several decades. The
chart below represents some of the latest imprisonment statistics from the Bureau of Justice
Assistance (BJA). According to the BJA, since 1978 the number of federal and state prisoners in
the US has gone from below 200,000 to just over 1.5 million (See Figure 1.1). While the last
several years has seen an encouraging downturn in the prisoner population, this represents a
staggering increase in the last several decades. Taking into account jail populations, about 1 in
every 108 adults was incarcerated in prison or jail at year end 2012 (Bureau of Justice Statistics,
2012). Even though other countries have also grown their prison populations over some of this
5
period, the United States stands out as an “overachiever” in this area. The Unites States has 5%
of the world’s population, yet the United States accounts for 25% of the world’s prison
population (Nagin, 2014).
Figure 1.1- The Growth of the US Prison Population
The reasons for the increase in the US prison population have been well documented.
Stricter sentencing policies, particularly for drug-related offenses, rather than rising crime, are
the main culprit behind skyrocketing incarceration rates (Schmitt, Warner, & Gupta, 2010).
Indeed, crime was on the rise during the period of the late eighties and early nineties when drug
courts first began to spring up. However, since that time, even as the total number of violent and
property crimes fell, the incarcerated population continued to expand rapidly (Schmitt et al.,
2010). There is also a social justice component of imprisonment in the US that cannot be
ignored. African-Americans are the most imprisoned group in the US. While African-
Americans comprise only 12% of the US population, this group comprises nearly 40% of the
nation’s inmates, with some researchers estimating that more than one in four African-American

6
men will spend time behind bars (Hetey & Eberhardt, 2014). Arrests for drug offenses remain
highly concentrated in urban African-American and Hispanic communities beset with high
poverty rates and other forms of concentrated disadvantage (Sevigny, Pollack, & Reuter, 2013).
This inordinate sentencing that makes the racial breakdown of US prisoners an inverse
representation of the general population is yet another reason why drug courts in urban, majority
African-American areas like Richmond such an important area of study.
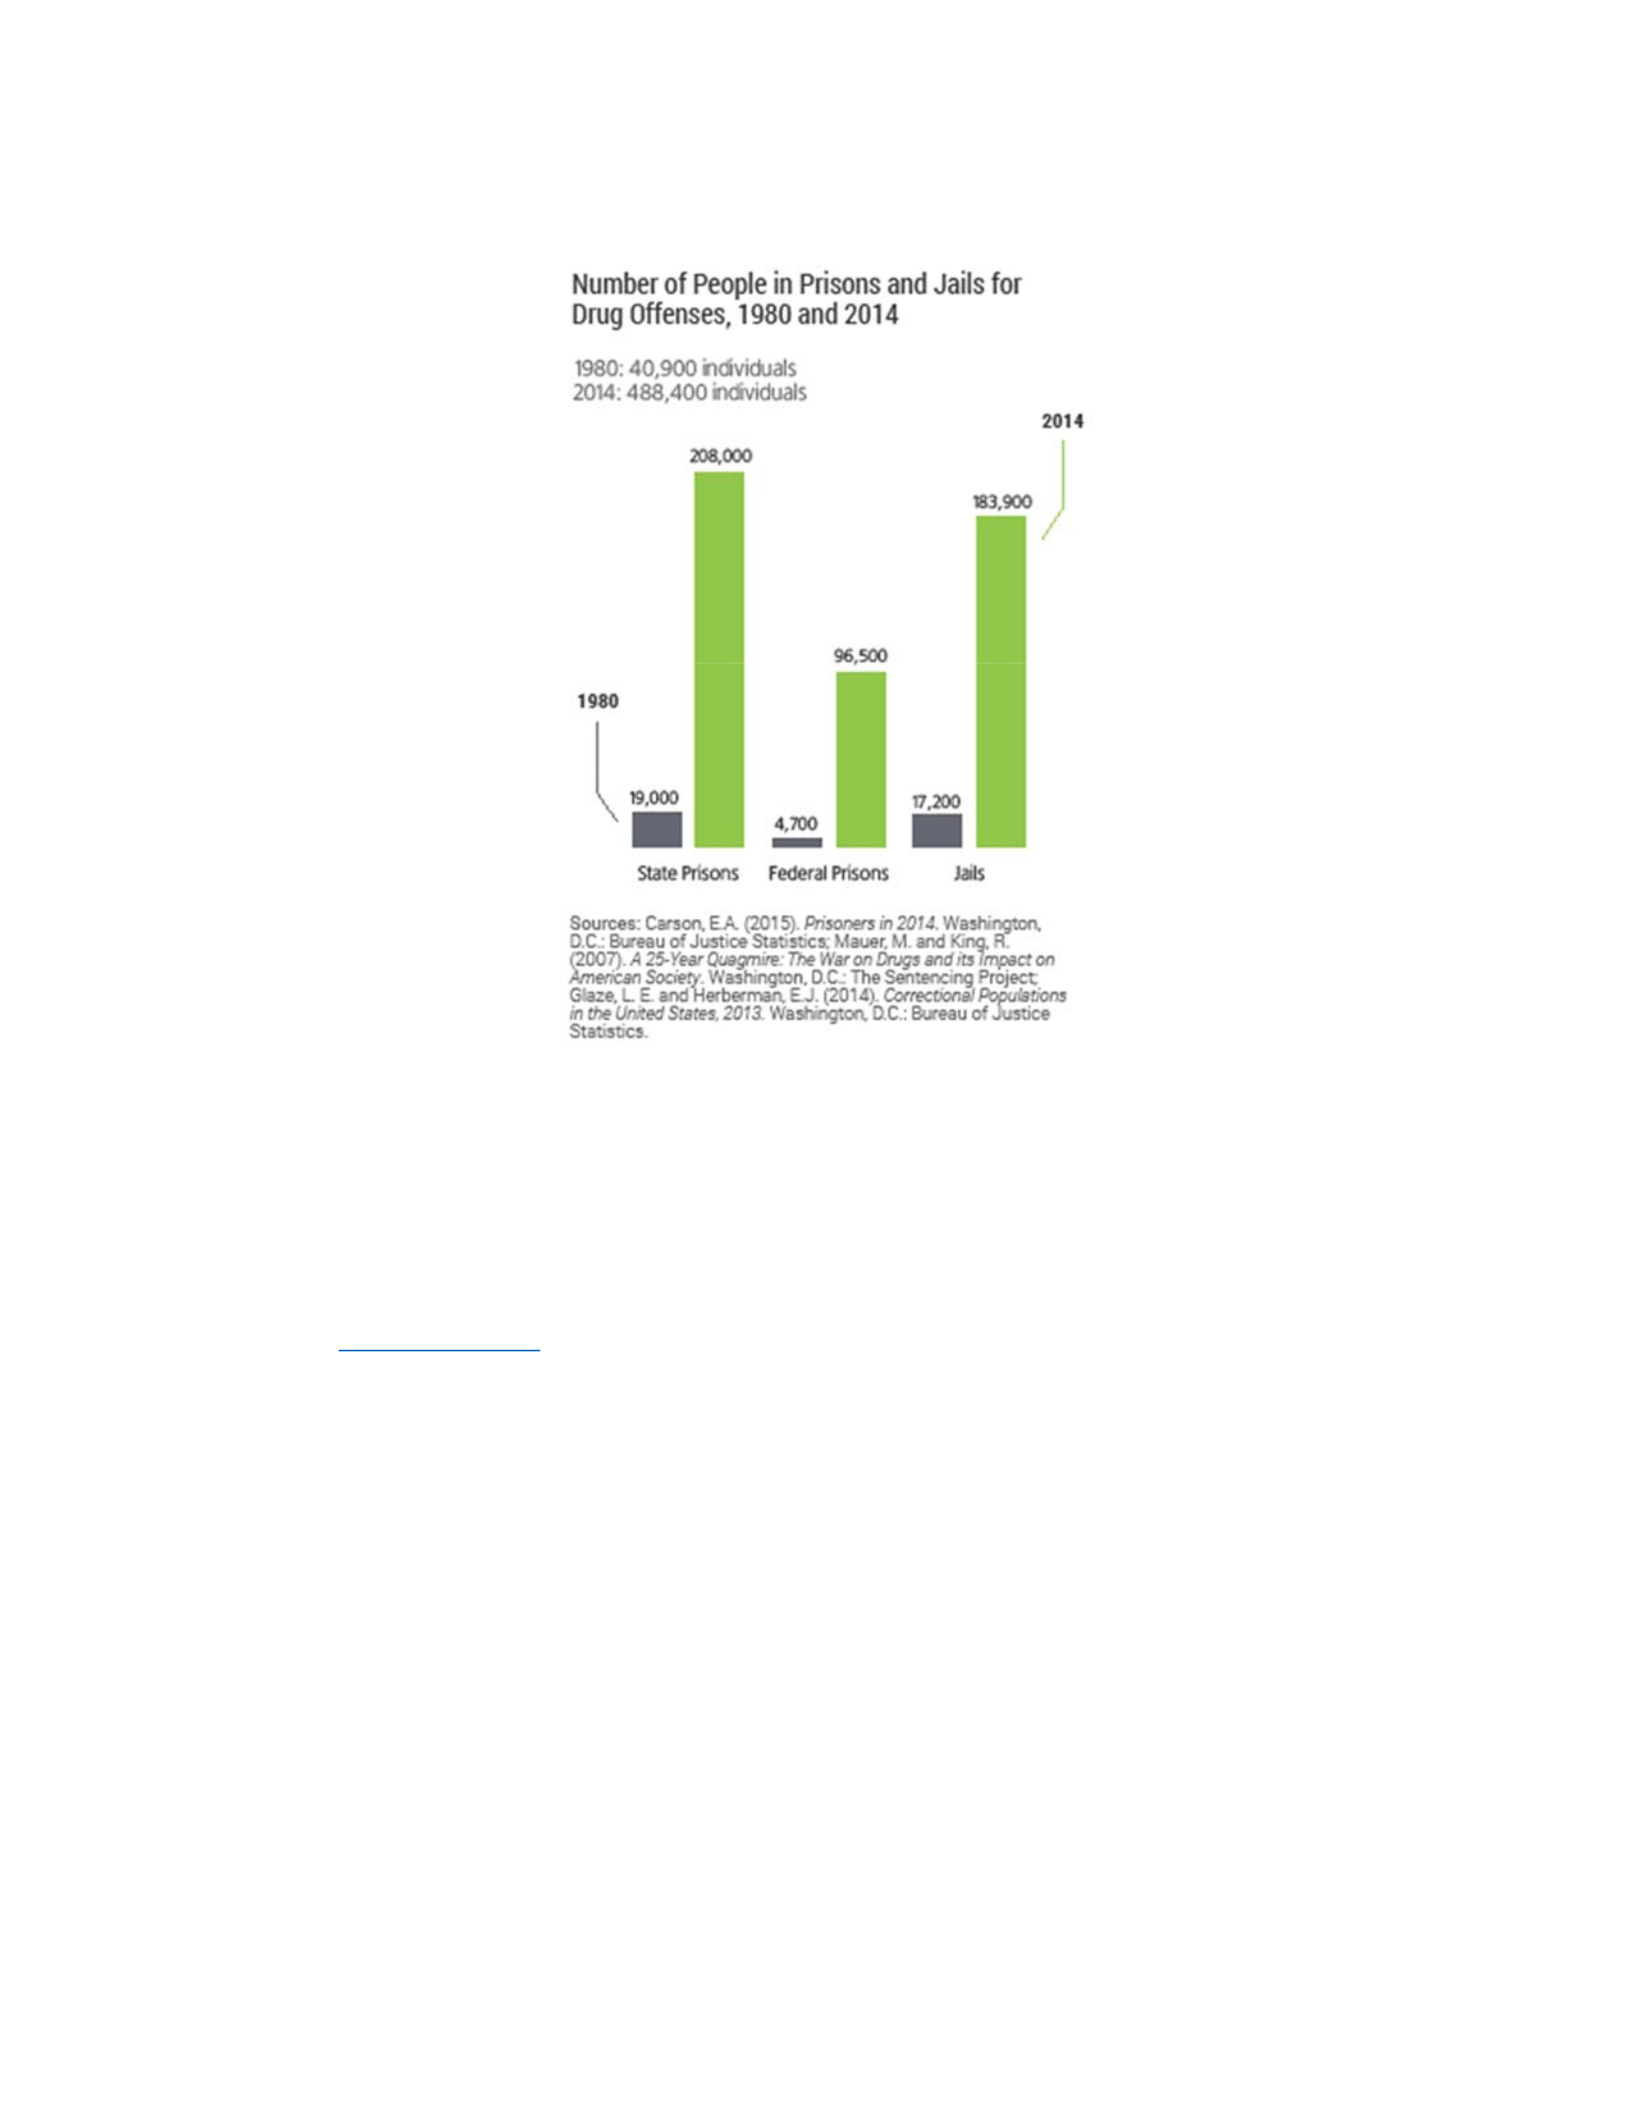
Drug offenses are also a major reason for the increase in the prison population. Figure
1.2 below illustrates the huge increase of people in prisons and jails for drug offenses between
1980 and 2014. The “war on drugs” has drastically increased incarceration rates since the 1980s,
as a growing number of drug-using offenders have been sent to prison and jail for ever increasing
length of sentences (Sevigny et al., 2013). While we have seen recent trends to reverse the rigid
and increasingly punitive sentences wrought by the drug war, much of the damage is done. Even
as measures like drug courts seek to impact the prison population, there is a generational problem
that may take decades to resolve.
7
Figure 1.2- Number of People Imprisoned for Drug Offenses
Troubling trends in drug abuse and substance use disorders further highlight the
intractable problems drug courts are attempting to address. According to the Centers for Disease
Control and Prevention (CDC), 105 people in the United States die every day from drug
overdoses (CDC.gov, 2016). Further, according to the National Institute on Drug Abuse
(NIDA), 38,329 Americans died from drug overdoses in 2010. That number is higher than the
31,672 killed that same year in the US by guns and higher than the 33,687 that died in US car
accidents (“Drug Overdoses Kill”, 2015). These numbers seem to draw far less concern than
recent public concern over gun violence and terrorism which kill fewer Americans.
It should be noted that there are huge numbers of Americans in need of substance use
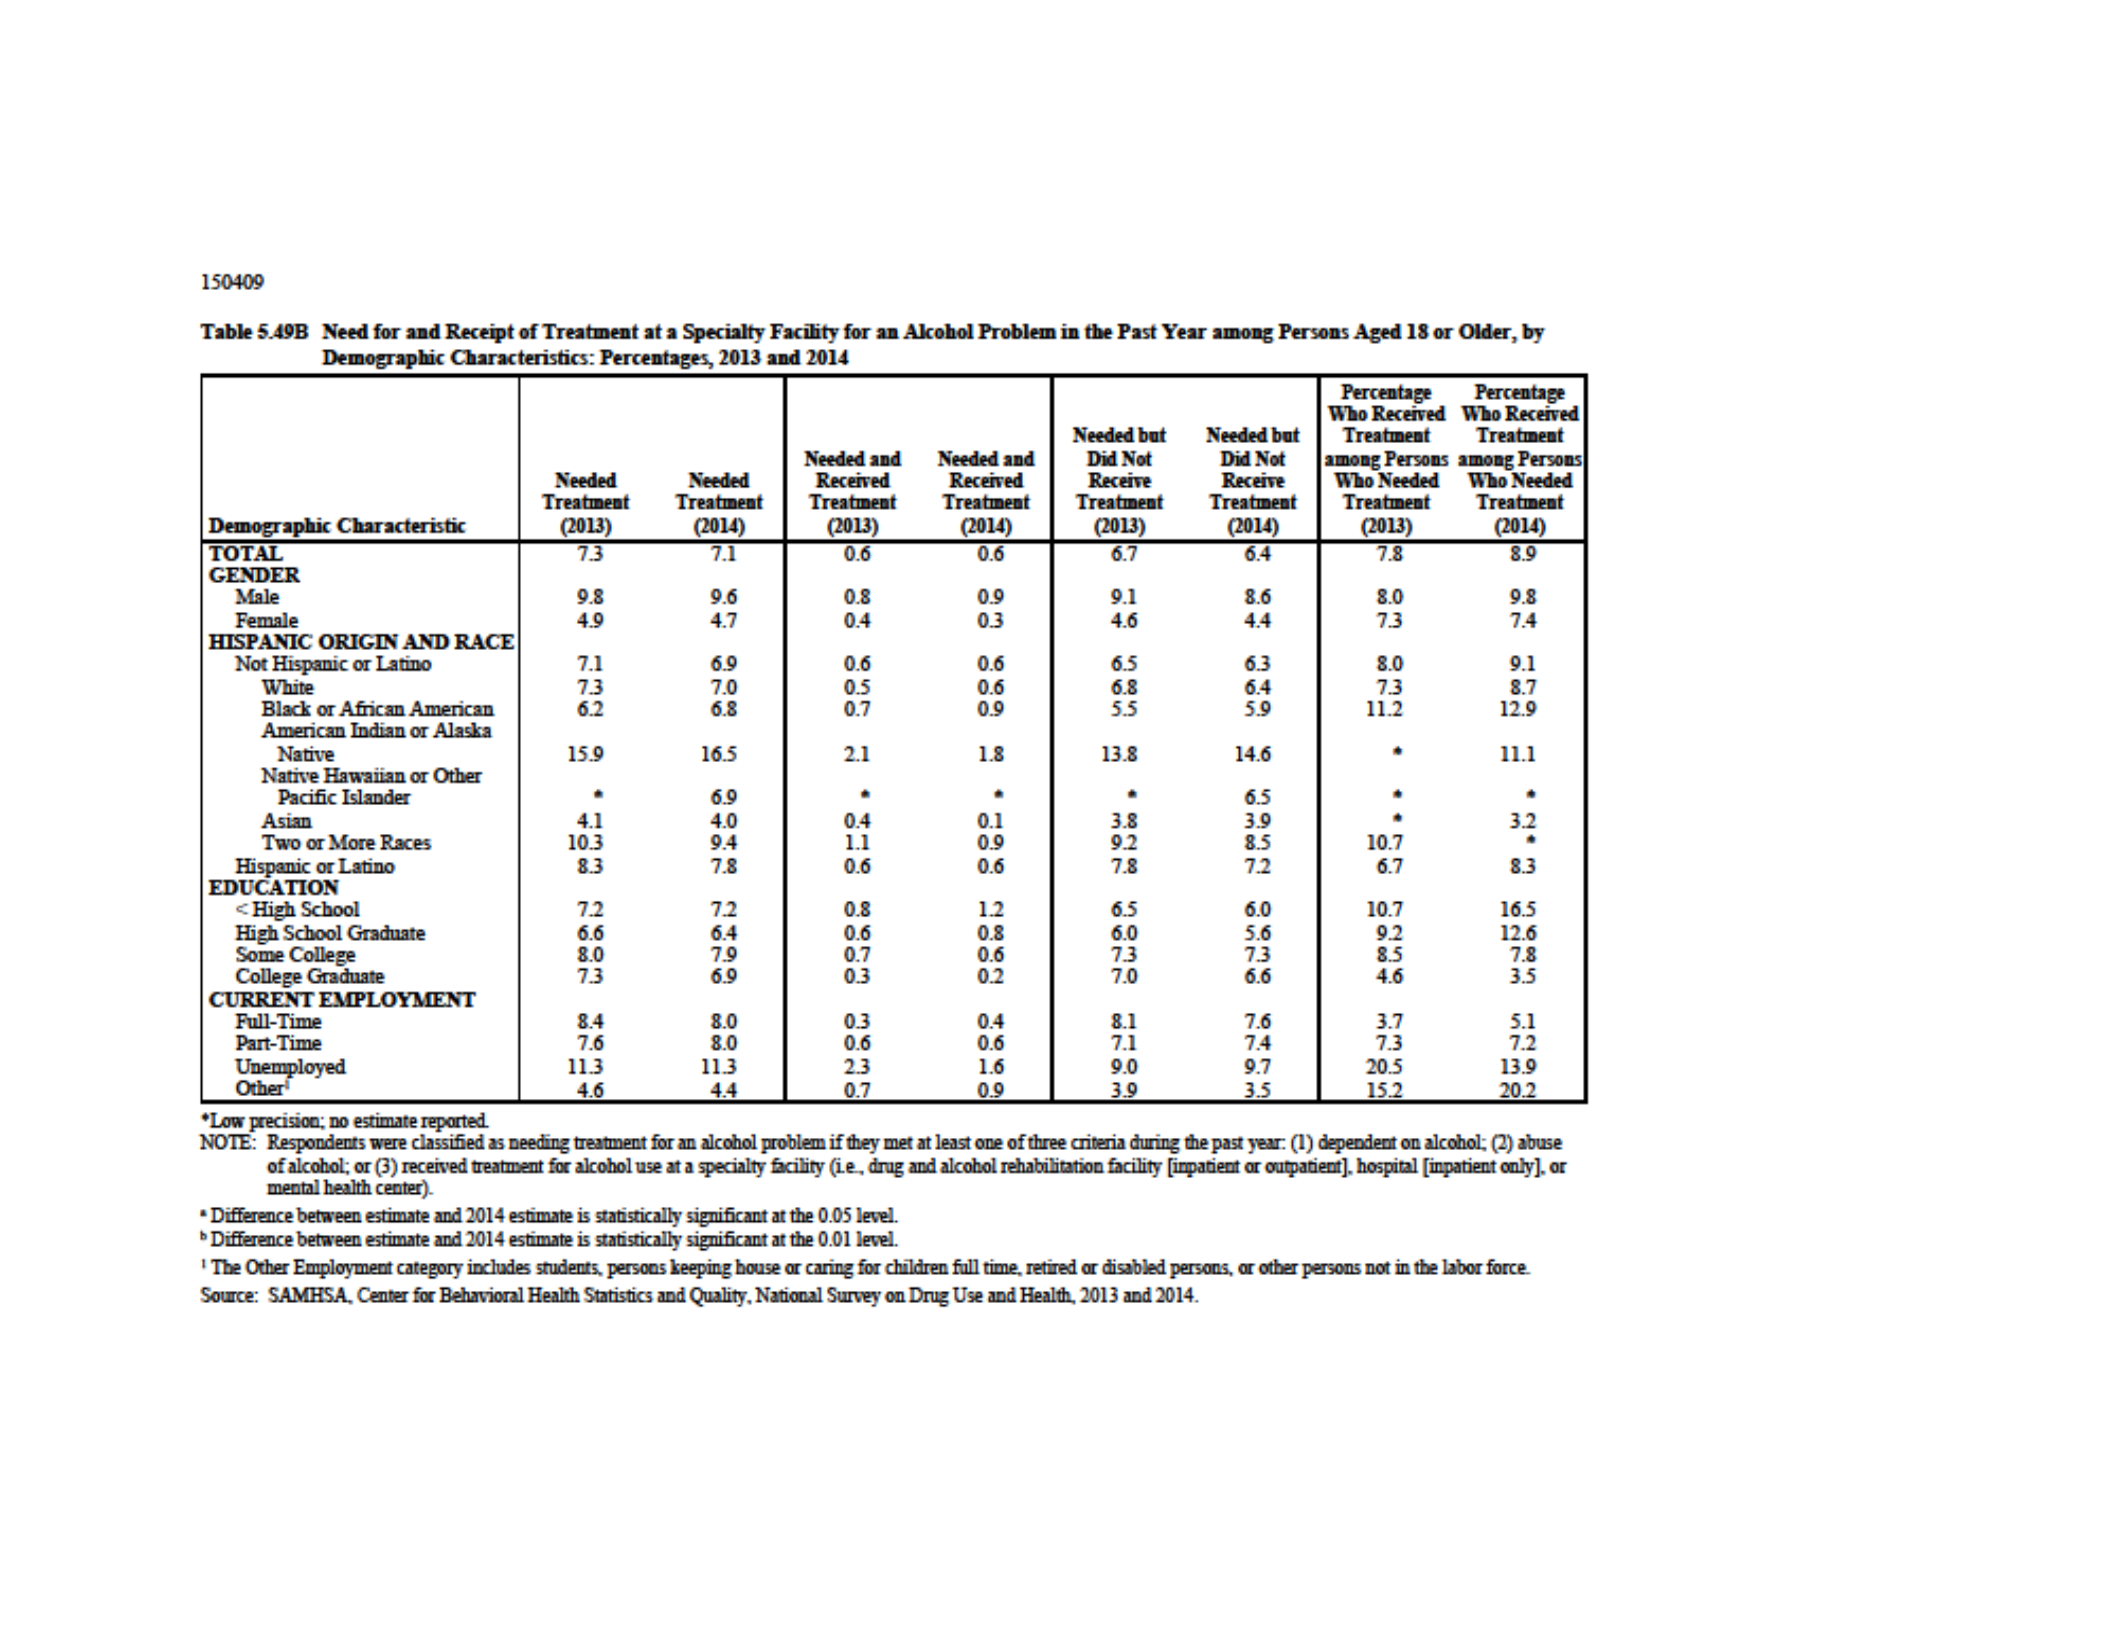
disorder treatment who are not receiving services or are receiving inadequate services. Figure
1.3 is a chart from the 2014 Substance Abuse and Mental Health Services Administration

8
(SAMHSA) national survey outlining the unmet need for substance abuse treatment in the US.
The chart below illustrates that, of those who needed substance use disorder treatment, only
8.9% received treatment in 2014—up from the previous year. Across all racial and ethnic
groups, a recent National Institute of Health (NIH) study found high rates of unmet need for
substance use treatment, with most estimates over 90% across all need definitions, regardless of
racial/ethnic category (Mulvaney-Day, DeAngelo, Chen, Cook, & Alegría, 2012). It is clear that the
gap between those who need treatment and those who get it is huge, illustrating further need to
think creatively in how and where substance use disorder treatment is delivered.
9
Figure 1.3- Unmet Substance Abuse Treatment Needs

Another national factor influencing the huge influx into prisons during the war on drugs
is discrepancy in sentencing for different forms of cocaine. The Anti-Drug Abuse Act of 1986
created harsher penalties for possession of crack cocaine than for the powdered form of cocaine
which resulted in a 100 to 1 sentencing disparity (Hessick & Andrew, 2010). Although the Fair
Sentencing Act of 2010 went a long way towards eliminating this disparity (Graham, 2011),
much of the damage had been done. Since the two forms of cocaine are pharmacologically
indistinguishable, by dictating harsher sentences for possession of crack than for possession of
powder, the law is more severely punishing the poor, who obtain the affordable form of cocaine
(crack), than the affluent, who obtain the more expensive form of the same drug (powder)
(Coyle, 2002). The implications of this policy on who goes to prison for cocaine use represent a
social justice issue that drug courts putatively help address.
With regard to the local area, according to the State Attorney General’s Office, heroin
overdose fatalities in Virginia have more than doubled from 100 deaths in 2011 to 239 deaths in
2014 (oag.state.va.us, 2015). The fatalities increase when examining just the last year of that
time period in which the number of fatal heroin overdoses in Virginia increased by 57.8% in
2013 compared to 2012, and represented 23.4% of all drug/poison deaths (Virginia Chief
Medical Examiner’s Office, 2014). The central region of Virginia (in which Richmond City is
located), had the highest number of fatal heroin overdoses in the state in 2013 (78, 36.6%) with
Richmond City having one of the highest rates of deaths from heroin overdose (21, rate of 9.8%).
There is a direct link between illicit drugs and crime. Over 80% of adult offenders in the
US misuse drugs or alcohol, meaning they were arrested for a drug- or alcohol-related offense,
were intoxicated at the time of their offense, reported committing their offense to support a drug
or alcohol problem or they have a significant history of substance abuse or substance abuse

11
treatment (Marlowe, 2015). Geographically, Interstate 95 transverses the city and is known as
the drug transportation corridor for the east coast. As illegal substances are being routed through
this region, the opportunity and likelihood for illicit drugs to be distributed or sold in this
community is increased. The metro Richmond area has been designated a HIDTA (High
Intensity Drug Trafficking Area) along with the Washington, DC and Baltimore regions since
2005 (“HIDTA Counties by State”, 2015). This designation is to some degree confirmed by the
disproportionate number of drug/narcotics arrests in Richmond as compared to rest of the state.
For persons 18 and over, the number of arrests for drug/narcotic offenses in Richmond (2,044)
represents 5.6% of the state total (30,464).
The human scope of these problems should be troubling enough, but there is also a
substantial financial cost to incarceration and drug abuse. A recent study by the VERA Institute
for Justice estimated that the total cost of imprisonment in just the 40 states participating in their
survey was over $38 billion (Henrichson & Delaney, 2012). Even setting aside the human toll of
incarceration, a small decrease in the number of individuals incarcerated would achieve
significant financial savings for taxpayers. When one includes the cost of illicit drug abuse to
the US, the numbers become truly staggering. According to the National Institute of Health
(“Trends and Statistics”, 2015), the overall costs to American society of illicit drug abuse is $193
billion. Taken together, the incarceration costs and societal costs approach $231 billion. This
amount is more than one third of the $668 billion (Walker, 2013) that the US spent on defense in
2012 (note that this is defense spending in a year that the US was conducting 2 active wars
overseas).

12
Purpose of This Study
The objective of this study is to identify particular aspects of the drug court intervention
and social/demographic aspects of drug court participants that contribute to success in
completing a drug court program. The secondary data set contains a wealth of information on
the participants in one particular program, captured at various time points, which provides a rich
picture of the participants in the program. The aim was to find particular aspects of the program
and participants that are statistically associated with graduation (successful completion) from the
drug court program. The intended outcome of this study is a statistical understanding of what
variables, selected for study based on theoretical guidance and the literature, have the highest
impact on graduation rates from drug court.
This study attempts to further the knowledge base of drug courts by isolating the most
effective elements of one particular drug court program. As drug courts proliferate throughout
the nation and participation in those courts increases, there is a need for and value in actionable
research. By demonstrating what works in drug courts and what potential risk factors are for
certain groups, drug court professionals can increase chances for success for all participants and
screen participants accordingly. Further knowledge of what contributes to drug court success
will also allow policy makers and clinicians to adjust programs for maximum success of
participants and allow for increased impact of an important criminal justice innovation.
Chapter 2 discusses more fully the theoretical grounding of this study. This study uses
Life Course Theory, Social Capital Theory and Recovery Capital Theory to account for inherent
demographic traits of participants and societal/judicial influence on drug court participants. This
study attempts to arrive at a conclusion that will merge the ‘macro’ and ‘micro’ in a way
consistent with the approach of social work and informative of the impacts of drug courts.

13
Implications for Social Work
The preceding data outlining prison statistics, drug use problems and the exploding costs
of these challenges make research of drug courts a natural fit for social workers and social work
scholarship. While drug courts have been widely addressed in criminal justice and substance use
disorder literature, the topic has been very sparsely addressed in social work literature. Tyuse
and Linhorst (2005) outline the ways in which social workers may interact with these courts:
[social workers] may be members of a task force that develops a specialized court, or
they may fill administrative or direct services positions in substance abuse, mental health,
or criminal justice agencies that are parts of the court system and network of service
providers. Social workers also may have sporadic contact with drug courts and mental
health courts, such as when a client or a client's family member encounters the criminal
justice system and has a substance abuse disorder or mental illness. (p. 238).
Tyuse and Linhorst further point out that regardless of what interactions social workers may have
with drug courts, that a working knowledge of the legal system and available local substance use
disorder treatment resources will aid them in serving their clients and improve their efficacy in
their profession.
Social workers must also be cognizant of the more general issues of the ever increasing
incarcerated population and the fact that it is reflective of vulnerable minority populations,
further marginalized by the presence of substance abuse issues. Social workers educated in
criminal justice matters in general and drug courts in particular are able to better advocate and
pursue social justice on behalf of clients affected by what has become an overwhelming societal
issue.

14
This vital and evolving area of study is just beginning to impact our society. There is a
great contribution to be made in going beyond the efficacy question and attempting to understand
the components of an intervention that was born of “muddling through” an intractable problem.
Indeed, by understanding why a drug court works, we can further hone what has already proven
to be an effective, holistic and more humane way of dealing with an enormous and complex
social problem.
Study Overview
Chapter two of this study begins with a review of the relevant literature on drug courts.
The literature review explores the current guiding principles of drug courts, the current
understanding of the effectiveness of drug courts, how drug courts have been performing from a
cost standpoint, current participation in drug courts and details of the drug court that is the focus
of this study. Chapter two closes with a review of the concept of Therapeutic Jurisprudence and
the theoretical foundation for this study—Life Course Theory, Social Capital Theory and
Recovery Capital Theory.
Chapter three begins with an overview of human subjects’ protection observed in this
study then moves on to a description of the instrument used to collect data, a brief discussion of
secondary data analysis, validity issues related to the data collection instrument, a description of
the independent and dependent variables and closes with the data analysis plan. Chapter four
presents the results of the study, and Chapter five contains a discussion of the results, limitations
discussion and implications for future research.

15
Chapter 2: Literature Review and Theoretical Grounding
Drug courts have been studied extensively since their inception in the late nineteen-
eighties. While the literature is extensive, the vast majority of study has been done in criminal
justice with precious little study in the social work field. The scarce social work study on this
subject was covered in chapter one. The following literature review outlines the current state of
the understanding of drug courts and what elements of drug courts are currently considered to be
potential factors for success. This review also includes an overview of the key elements of drug
courts and some of the current, universally accepted tenets of drug courts. An overview of the
Richmond Adult Drug Court also ties the court in which this study occurred to the larger drug
court movement.
Following the literature review is an overview of the theoretical basis for this study, Life
Course Theory, Social Capital Theory, Recovery Capital Theory and a conceptual model
outlining how those theories are applied in this study. Theory, as simply defined by Frankfort-
Nachmias & Leon-Guerrero (2010), is an elaborate explanation of the relationship between two
or more observable attributes of individuals or groups. Using life course theory, this chapter
establishes a theoretical model to serve as the basis of this study. The theoretical model
establishes a paradigm, or basic set of beliefs that guides action (Guba, 1990). The theoretical
model outlined in this chapter attempts to understand the myriad micro and macro influences on
drug court participants and both demographic and justice system factors influencing success. By
attempting to find influencing factors, understood through the prism of life course theory, this
study will attempt to find links between those influences and success in drug court programs.
16
Drug Court Basic Components and Evidence of Efficacy
The foundation of almost any drug court program in the US is the 10 Key Components of Drug
Courts, as defined by the National Association of Drug Court Professionals (NADCP):
Figure 2.1 10 Key Components of Drug Courts
1. Drug courts integrate alcohol and other drug treatment services with justice system case
processing.
2. Using a nonadversarial approach, prosecution and defense counsel promote public safety
while protecting participants’ due process rights.
3. Eligible participants are identified early and promptly placed in the drug court program.
4. Drug courts provide access to a continuum of alcohol, drug, and other related treatment
and rehabilitation services.
5. Abstinence is monitored by frequent alcohol and other drug testing.
6. A coordinated strategy governs drug court responses to participants’ compliance.
7. Ongoing judicial interaction with each drug court participant is essential.
8. Monitoring and evaluation measure the achievement of program goals and gauge
effectiveness.
9. Continuing interdisciplinary education promotes effective drug court planning,
implementation, and operations.
10. Forging partnerships among drug courts, public agencies, and community-based
organizations generates local support and enhances drug court program effectiveness.
(“13 Key Principles, 2015)
More recently, the International Association of Drug Treatment Courts (IADTC) adopted the 10
Key Components but added three components focusing on the social reintegration of
participants, ensuring flexible treatment for indigenous populations and ethnic minorities, and
planning for aftercare recovery services (Marlowe, 2015):
17
Figure 2.2: Additional 3 Drug Court Components
1. Ongoing case management includes the social support necessary to achieve social
reintegration.
2. There is appropriate flexibility in adjusting program content, including
incentives and sanctions, to better achieve program results with particular
groups, such as women, indigenous people and minority ethnic groups.
3. Post treatment and after-care services should be established in order to enhance
long term program effects.
(“13 Key Principles, 2015)
While it should be noted that most US drug courts still adhere to the 10 Key components
outlined above, that in practice, if not in stated purpose, the three additional components are
observed in many US drug courts including the Richmond Adult Drug Court where data for this
study was collected.
These components combine to form individualized interventions that simultaneously
provide drug treatment to drug abusing offenders and hold them accountable for their behavior
(Mitchell, Wilson, Eggers, & MacKenzie, 2012). It is important to understand that drug courts
emerged without a solid theoretical basis and it would be fair to say that drug court policy was
developed using the classic policy development description from Lindblom (1959) of “muddling
through.” It is interesting, albeit common in the criminal justice system, that drug courts’ initial
expansion occurred without a solid body of empirical evidence establishing their effectiveness in
reducing criminal behavior (Mitchell et al., 2012).
One can find a range of opinions on drug courts from definite contentions that “drug
courts work” (Meyer & Ritter, 2001) to contentions that there is a “lack of evidence supporting
the effectiveness of drug courts” (Anderson, 2001). This author contends that drug courts should

18
be considered yet another intervention, albeit with the force of the judicial system behind it. In a
summary of existing drug court research the General Accounting Office (GAO) states:
Some studies showed positive effects of the drug court programs during the period
offenders participated in them, while others showed no effects, or effects that were
mixed, and difficult to interpret. Similarly, some studies showed positive effects for
offenders after completing the programs, while others showed no effects, or small and
insignificant effects. (Wilson, et al., 2006)
It seems with any intervention, the more extensive the literature on that intervention, “the greater
the likelihood that it will contain conflicting findings that can lead researchers to different
conclusions” (Marlowe, 2004).
However, the vast majority of literature reviewed by this author points to the efficacy of
drug courts and the superior outcomes in drug courts as compared with traditional, punitive court
models. Some authors, particularly (Whiteacre, 2004) make valid points regarding a great deal
of the drug literature with criticism that there are fatally flawed sampling methods. However,
randomized experimental designs conducted in the Maricopa County (Ariz.) Drug Court (Turner
et al., 1999), the Baltimore City Drug Treatment Court (D. C. Gottfredson, Najaka, & Kearley,
2002)(D. C. Gottfredson & Exum, 2002), and the Las Cruces (New Mexico) DWI Court
(Breckenridge et al., 2000) all point to the success of drug courts. Although drug courts enjoy
empirical support, the fact remains that some drug courts “work” better than others (Shaffer,
2011). One goal of this study is to understand what elements contribute to drug court success in
an attempt to expand the knowledge base of what does “work,” and how success can be
replicated.

19
One of the glaring issues facing drug court research is that of generalizability. It could be
argued that it is almost impossible to get a scientifically accurate picture of how effective drug
courts are due to variations in how they operate nationwide. Differences exist on who is eligible,
how they are selected, what treatments are available and, very importantly, how court practices
affect the outcome (Harrell, 2006). Longshore, et al. (2001) does attempt to provide a five-
dimension framework for operationalizing drug court practices. Longshore, et al., attempt to
define the five key dimensions of drug courts by creating a scale to measure:
1. The Degree of Leverage. This dimension is a measure of how much leverage
(i.e.: possibility of serious punishment for non-participation or for failure to
complete the program.
2. Population Severity. This is a measure of the severity of the population both with
level of addiction and criminal background.
3. Program Intensity. This is a way to gauge how intense treatment and other
services (such as employment assistance or housing assistance) are in a particular
program.
4. Predictability. This scale asks how predictable and/or consistent sanctions and
rewards are in any drug court program.
5. Rehabilitation Emphasis. This measure asks how much the punitive versus
rehabilitative aspects of the program are emphasized.

20
While the framework developed by Longshore et al. does provide for some useful tools to
compare different programs, it can still be argued that drug courts could benefit by finding a way
to implement evidence-based standardized practices nationwide. Thus, making it easier to
aggregate and interpret many wildly different drug court statistics and making a case that the
public and lawmakers could easily understand. This author would argue that another vitally
important factor contributing to the generalizability of drug court research (which Longshore et
al. do not address) is the varying array of treatments available. Different areas have differing
resources and treatment providers. While this study, by design and necessity, focuses on one
drug court out of thousands worldwide, the aim is —with the aid of theoretical approaches
discussed later in this chapter—to arrive at concretely generalizable factors that help drug courts
succeed.
Cost Effectiveness of Drug Courts
Most observers would agree that drug courts are a more humane and proactive way to
deal with lower level drug offenders in the criminal justice system. However, an added benefit is
their long term cost effectiveness. A study by Carey et al., (2008) found drug courts achieved a
significantly lower per-person taxpayer investment than traditional criminal justice measures.
Another study by Lowenkamp, Holsinger, & Latessa (2005) found a total of $2,328.89 is saved
per participant in outcome costs. That study further found that, if victimization costs (property
damage, etc.) are included, that number rises to $3,596.92 per offender. Taking off the table
differing ideologies with regard to how best to deal with drug crime, those numbers are
compelling from any standpoint.

21
A study by Bhati, Roman, & Chalfin (2008) found that of the almost 1.5 million arrestees
at risk of drug abuse or dependence, 109,921 (about 7%) met drug court eligibility requirements.
Of the 109,921 eligible, approximately half (55,364) were actually enrolled in a drug court
program. In aggregate, just 3.8% of the at-risk arrestee population was treated in drug court.
Drug courts as an intervention have a large and growing body of literature pointing to their cost
effectiveness and success in preventing recidivism. The numbers of individuals participating in
these programs can and should grow. Studies like this one helping to further isolate the effective
components of drug courts, and isolating which people are more likely to succeed, will help to
further institutionalize and grow drug courts.
The Richmond Adult Drug Court
The variation in drug courts throughout the nation necessitates some familiarity with the
drug court that is the subject of this study. Appendix 1 to this study is the handbook for the
Richmond Adult Drug Treatment Court (RADTC). The drug court model emphasizes formal
contractual agreements between the participants, mental health service organizations, and the
court system. In this treatment modality, the judge, prosecuting attorney, defense counsel, and
participant agree that the participant will complete a program that is approximately one year long
and contains three, 4-month “phases” (Stein, Deberard, & Homan, 2013). The RADTC program
incorporates the phases model via a five phase, highly structured, outpatient treatment program
that lasts a minimum of 16 months. The length of the phases varies depending upon individual
progress. The five phases of the RADTC as outlined in their manual are
Evaluation/Probationary Period (approximately 30 days), Phases 1 through III each lasting

22
approximately 17 weeks and an aftercare component (approximately 6 months for the period
post-graduation).
The phases of the RADTC are a reflection of the general course of most drug court
programs. The early phases of RADTC drug court reinforce the importance of abstinence and
social connection by requiring the following:
Secure employment or enrollment in school. Failure to obtain employment, or remain
employed or enrolled in school, will result in daily reporting for group sessions and/or
community service;
Attend the required number of recovery group meetings per week [e.g., twelve step
AA/NA];
Secure a home group and a sponsor;
Oral and/or written presentation of an acceptable first step;
Attendance at a minimum of fifty-one (51) group sessions with satisfactory group
participation;
Meet weekly with designated staff as directed;
Attendance at all scheduled groups and individual sessions, recovery group meetings and
drug screens (no missed sessions for thirty (30) days prior to phase movement);
Submit to drug screens as directed by staff;
Participate in recreation and fellowship activities;
Appear in court as required;
Completion of 15 hours of community service;
Make timely payments of Drug Court fee
(Participant Manual, 2016)
The RADTC phases are explained in full in Appendix 1 and summarized briefly in Table 2.1
below. The phases are progressively less restrictive as time passes with drug testing decreasing
in frequency and fewer face to face interactions required of participants.

23
Table 2.1
Drug Court Phases
Phase Duration
Evaluation/Probationary Period 30 Days
Phase I Approximately 17 Weeks
Phase 2 Approximately 17 Weeks
Phase 3 Approximately 17 Weeks
Aftercare Approximately 6 Months
There is also a graduated sanction grid that is in keeping with the key components of drug courts
and generally accepted drug court principals. The following 2 pages contain the sanctioning
grids for the RADTC.
24
Table 2.2
RADTC Sanction Grid
ACTION
1ST INCIDENT
2ND INCIDENT
3RD INCIDENT
4TH + INCI`DENT
MISSED 12 STEP
/ RECOVERY
MEETINGS
8 hours of
community service.
Meetings must be
current by the next
week
16 hours of
community service
No credit for group
until meetings are
current
2 days in jail
No credit for
group until
meetings are
current
5 days in jail + restart
current phase
Meet with treatment
team
FORGED/
ALTERED DRUG
COURT
DOCUMENTS
3 days in jail for
each forged
document
Revocation from
the program and
CA will
recommend active
incarceration
DRUG/
ALCOHOL
TESTING AND
TAMPERING
Late, Missed
Screens, Unable to
give, Adulterated,
Diluted screens
Each participant is
responsible for
submitting a
sample that is able
to be tested. Dilute
screens will be
considered positive.
5 days in Jail
5 additional days in
jail will be received
if the participant
tests positive for
the entire week
Possible referral
for
Detox/Inpatient/ or
STEP UP & OUT
10 Days in Jail
5 additional days in
jail will be received
if the participant
tests positive for
the entire week
Possible referral for
Detox/Inpatient/ or
STEP UP & OUT
20 days in Jail
5 additional days
in jail will be
received if the
participant tests
positive for the
entire week
Possible referral
for
Detox/Inpatient/
or STEP UP &
OUT
30 days in jail
Possible referral for
Detox/Inpatient/ or
STEP UP & OUT
5th INCIDENT
Minimum of
45 days, STEP UP &
OUT,
or
Revocation from the
program. CA will
recommend active
incarceration.

25
Table 2.2 Cont.
RADTC Sanction Grid
ACTION
1ST INCIDENT
2ND INCIDENT
3RD INCIDENT
4TH + INCIDENT
MISSED
GROUP &
INDIVIDUAL
TREATMENT
SESSION
Excused missed
sessions will be
made up
8 hrs. In- House
Community Service
Missed session will
be made up within a
week
3 days in jail
+written or oral
presentation
Missed sessions
will be made up
within a week
5 days in jail
Missed sessions
will be made up
within a week.
Revocation from the
program. CA will
recommend active
incarceration
MISSING JOB
SEARCH FORMS
Verbal reprimand
Job deadline
2 days in jail
5 days in jail
FAILURE TO
SUBMIT THE
REQUIRED
HOURS FOR
EMPLOYMENT,
EDUCATION,
AND/OR
COMMUNITY
SERVICE
3 days in jail
6 days in jail
Meet with
treatment/
probation team
9 days in jail
Meet with
treatment/
probation team
Revocation from the
program. CA will
recommend active
incarceration
CURFEW
VIOLATION
Indefinite 8p
Curfew
**2 days in jail if
out the entire night
3 days in jail +
Indefinite 8p
Curfew
5 days in jail +
Indefinite 8p
Curfew
Revocation from the
program. CA will
recommend active
incarceration
PROVIDING
FALSE
INFORMATION
TO STAFF
ABOUT
MATERIAL
FACTS
e. g., residence,
employment
3 days in jail
5 days in jail
10 days in jail
Revocation from the
program. CA will
recommend active
incarceration

26
LATE TO
COURT
SANCTIONED AT THE DISCRETION OF THE JUDGE
An examination of the phases and sanctioning grids of the RADTC shows that not only
are most of the key components of drug court present in the RADTC but also key components of
social connection and social control. A major focus of RADTC interventions is to build social
bonds with judges, treatment providers, aftercare sponsors, and other former drug users who
have decided to participate in this voluntary intervention. The RADTC also attempts to locate
employment and encourage stable home lives for their participants. Offenders who participate in
these programs are clearly presented with an opportunity for major life turning points (Sampson
& Laub, 2005). This notion of connection to society and social control leads to the theoretical
grounding for this study.
Therapeutic Jurisprudence
As a concept, therapeutic jurisprudence is still relatively new. Professor David Wexler
first used the term in 1987 in a paper delivered to the National Institute of Mental Health (Hora,
Schma, & Rosenthal, 1998). Nailing down an exact definition of Therapeutic Jurisprudence is
not as straightforward a task as it would seem at first. A solid working definition is given by
(Winick & Wexler, 2001) who describe it as an interdisciplinary approach to legal scholarship
that has a law reform agenda. Therapeutic jurisprudence seeks to assess the therapeutic and anti-
therapeutic consequences of law and how it is applied. When they were first created, the
founders of drug treatment courts gave little thought to a theoretical or jurisprudential basis for
them (Fulton, Hora, 2002). Therapeutic Jurisprudence has emerged in public policy not as a
theory but more as a framework for approaching a common goal of a more comprehensive,

27
humane, and psychologically optimal way of handling legal matters (Daicoff, 2000). From the
movement of Therapeutic Jurisprudence, numerous problem solving courts have emerged
including specialized courts for DWI, Mental Health, Domestic Violence and others.
The different courts that have emerged from this movement, including drug courts, seek
to solve social problems using the principals of Therapeutic Jurisprudence applied in a variety of
ways in a variety of circumstances. In the case of drug courts, there is a commonality with other
problem solving courts in that cases brought before these courts require the courts not just
resolve disputed issues, but also attempt to solve a variety of human and social problems that are
responsible for bringing the case to court (Winick, 2002). With regard to drug courts, the
problems to be addressed are mainly addiction and societal disconnection that have led to
patterns of criminal involvement and ongoing interactions with the judicial system. These courts
grew out of a realization that traditional approaches such as three strikes and stringent sentencing
guidelines had failed to have the impact that policymakers had hoped.
In response to the failure of courts to actually reduce addiction, recidivism and criminal
behavior, the framework of Therapeutic jurisprudence offered a new option for attacking the
roots of these problems rather than simply “locking them up and throwing away the key.” The
new problem solving courts are all characterized by ongoing, active judicial involvement, and
the explicit use of legal authority to motivate participants to avail themselves of needed
services—at least in the eyes of the judicial system—and to monitor their compliance and
progress (Winters, Fals-Stewart, O'Farrell, Birchler, & Kelley, 2002). The key components of
drug courts reflect this approach and go a long way towards codifying what Therapeutic
Jurisprudence is within the context of drug courts. Dorf & Sabel (2000) describe this approach

28
as “experimentalist institutions” that point one way beyond the conventional limitation of courts
and other institutions.
Drug courts also represent a unique interaction between centralized and localized
authority that has been a hallmark of Therapeutic Jurisprudence. While the drug court
movement can certainly be seen as nationwide, judged by the proliferation throughout the
country and world, the workings, interventions and operation are uniquely customized at the
local level. This localization, and even customization, of drug court programs means that even
factors such as a judge’s personal style can impact the effectiveness of the Therapeutic
Jurisprudence model. In support of this notion, a study by the NDCI found that better outcomes
were produced, for example, by drug courts that had moderately predictable sanctioning
schedules, exercised greater leverage over their participants, and had judges with more positive
interactional styles (“Drug Court Review”, 2015). This frequent drug court “customization” and
dependency on personnel is a challenge to drug court research that will be discussed further in
Chapter 5.
No social work discussion of Therapeutic Jurisprudence would be complete without an
examination of human rights and the rights of the individuals participating in drug court
programs. It has been debated as to whether Therapeutic Jurisprudence ought to be neutral (a
theory) or normative (a philosophy) (Birgden, 2015). The commitments of social work to the
concept of self-determination is well documented in the National Association of Social Workers
(NASW) Code of Ethics. However, it should be noted that the rights of self-determination even
within the NASW code are not absolute. The NASW Code states that “Social workers may limit
clients’ right to self-determination when, in the social workers’ professional judgment clients’
actions or potential actions pose a serious, foreseeable, and imminent risk to themselves or

29
others” (NASW Code of Ethics, 2015). Does this code include the scope of work in drug courts
that can be seen by many as paternalistic? This author would argue that in a blended system like
that of drug courts, drawing on numerous disciplines each with their own code of ethics, that no
single professional code of ethics will be fully represented. This is inherent to social work in any
setting, and indeed, any professional code of ethics (Senjo & Leip, 2001).
Life Course Theory
One challenge in assessing the characteristics of effective drug courts is the lack of a
theoretical framework for their initial design and implementation (Shaffer, 2011). A laser like
focus on efficacy is understandable from a policy standpoint. But, beyond understanding whether
specialized court programs ‘work’, it is important to understand the mechanisms and theoretical
explanations for why they work (Kaiser & Holtfreter, 2015). Life Course Theory offers a
theoretical framework to understand why drug courts work and what factors of the drug court
intervention should be emphasized and studied. As reviewed earlier in this chapter, there has
been a wealth of study on “if drug courts work”, but far less study on the question of “why they
work”. By viewing the drug court intervention through the prism of Life Course Theory, we can
begin to ask informed questions about the elements of it and elements of the participants to gain
a richer understanding of the mechanisms by which drug courts get results.
Generally, Life Course Theory aims to connect the social meanings of age throughout the
lifespan, the intergenerational transmission of social patterns and the effects of social history and
social structure to study human behavior over time (Newburn & McLaughlin, 2010). The theory
concerns itself with structural factors such as poverty or racism and how those affect the
development of social bonds. In other words, the Life Course perspective integrates the micro

30
and macro factors to explain criminal behavior in a way that uses sociological, psychological and
aspects of human agency that are particularly compatible with social work. Another hallmark of
Life Course Theory in the context of criminal behavior is the labeling process (Newburn &
McLaughlin, 2010) that can lead to accumulating disadvantage over the course of the lifespan.
Life course research describes and explains constancy and modification in behavior or
over time, and life course study often focus on the timing, order, and degree of life events and
their influence on social development. Biological, psychological, cognitive, and social
developments occur on different time scales, each with their own significant transitions and
turning points (Halfon & Hochstein, 2002). This approach holds that life experience and
behavior can be understood by taking into context how a particular life trajectory came to be, and
how criminal behavior and drug use (with its intertwined biological, social and psychological
components) can influence offenders’ behaviors and decision making.
Trajectories, transitions, and turning points are key concepts in life course research (Hser,
Longshore, & Anglin, 2007). The primary aspect with which this study concerns itself is drug
court as a structural turning point (Newburn & McLaughlin, 2010; Elder Jr & Giele, 2009;
Green, 2010) in the lives of offenders that can substantially alter future trajectories. Sampson &
Laub (2003) found that job stability or marital attachment factors in adulthood were significantly
related to changes in adult criminal behavior—the stronger the adult’s ties to work and family,
the more likely an individual was to desist from criminal behavior. Social-control variables play
a key role in explaining desistence from crime and substance use among adult offenders
(Gottfredson, Kearley, Najaka, & Rocha, 2007). More specifically, strong social bonds to the
family and labor force were predictive of less crime and deviance among both delinquents and
nondelinquents (Gottfredson, Kearley, Najaka, & Rocha, 2007). Short of these social control

31
variables and bonds to normative society, individuals have been dubbed “life-course persisters”
(Sampson & Laub, 2005) will continue to offend, use drugs and make choices that have them
continually involved in the criminal justice system. These social controls, coupled with daily
routine activities that change from the unstructured to a routine filled with prosocial
responsibilities, helps foster a shifting in priorities away from deviancy towards conformity or
‘desistance by default’ (Barak, 1998). This author would argue that drug court is a disruptive
factor of the life course that fosters just that sort of turning point compatible with Life Course
Theory.
Although most of the research relating social bonds to desistence from crime and
substance use has focused on the importance of family and work as sources of social control,
theorists have suggested the importance of other opportunities for encouraging strong social
bonds. Sampson and Laub (1993) theorized that extended periods of incarceration potentially
reduces social bonds and might increase subsequent offending. They recommend that
alternatives to incarceration be used with offending populations, especially if these alternatives
include elements likely to increase attachments to the social order. Drug courts represent just
such an alternative. Put differently, locking them up and throwing away the key may not be the
best approach if the goal of the criminal justice system is to actually address root causes of
substance abuse and crime. A less punitive approach, operationalized in problem solving courts,
may be the way to better address crime and substance abuse.
Social Capital Theory
A brief discussion of Social Capital Theory is appropriate at this point as the notions of
the choices individuals make in the context of the life course can be linked to the idea of social

32
capital. That is, one may consider that acquired social capital is a necessity for attainment of
certain life milestones (in this case consider achieving abstinence and drug court graduation).
Therefore, the more social capital one acquires, the more resources (financial, emotional,
cultural) that person would have to devote to attaining drug court graduation. The first
systematic analysis of Social Capital was produced by Pierre Bourdieu who defined the concept
as “the aggregate of the actual or potential resources which are linked to possession of a durable
network of more or less institutionalized relationships of mutual acquaintance or recognition”
(Portes, 2000). Taking Bourdieu’s theory and applying it in the setting of drug courts requires
some thought as to how social capital is acquired. By accepting a new set of norms via factors
like socially connecting, severing connections to criminal culture and positive interactions with
the judicial system, drug court participants build social capital apart from their previous networks
and associations. Leveraging and accepting this new social capital and new social norms would
then allow these individuals to move forward with life changing consequences.
It could be argued that criminal behavior has an inverse relationship with social capital
“since social capital reflects the existence of cooperative norms, social deviance ipso facto
reflects a lack of social capital” (Fukuyama, 2001; May, 2008). An excellent expression of
social capital perspective in a drug court setting comes from (May, 2008) when she expresses the
concept that individuals who are engaged in social networks that normalize substance use have
“access to social capital that enables them to abuse or continue abusing substances”. The social
capital in this setting, May argues, is access to substances, a culture of substance use, and
normalcy about addiction, substance use, and criminal behavior. Therefore, upon release from
incarceration or while on probation or parole, drug offenders re-engage in social networks that
enable and foster maladaptive behavior. Hence, drug court immerses (and compels) individuals

33
to develop new forms of social capital based on normative behavior and new social bonds which
build ‘socially acceptable’ social capital via activities like employment, abstinence and
connection to the mainstream economic culture of non-offenders.
When thinking in terms of Social Capital Theory, drug courts can be seen as “factories”
that manufacture social capital. By providing access to services such as education, healthcare,
employment assistance, housing assistance and positive, abstinent social interactions, these
courts assist participants in building social capital. Ties to other, maladaptive social networks
are weakened and, in a combination of their own agency and decision making coupled with
compulsory/enforced rules and norms, change is achieved. Forming a new peer group, new
social connections and changing the patterns of addiction are all ways in which new social
capital is built. “The result is access to social capital that encourages conventional, prosocial
behaviors and facilitates an enhanced quality of life” (May, 2008).
Recovery Capital Theory
The theoretical construct of Recovery Capital (Cloud & Granfield, 2008) attempts to
expand upon the idea of social capital in a context more narrowly defined to apply to individuals
in recovery from substance use disorders. It can be understood by viewing it in the more familiar
context of risk and protective factors frequently used by clinicians in diagnosing and treating
those with substance use disorders. The components of Recovery Capital as defined by Cloud
and Granfield (2008) are:
Social Capital
Physical Capital
Human Capital

34
Cultural Capital
Social Capital in the context of Recovery Capital hews close to the definition in the widely used
notion of the theory. In essence, those with more Social Capital have group membership and
other resources to help improve their situation in a crisis (such as a substance use disorder).
Physical Capital in this context can easily be understood in terms of wealth and economic
resources. Human Capital embodies a wide range of individual attributes that provide one the
means to function effectively in contemporary society (Cloud & Granfield, 2008). This Human
Capital may include knowledge, skills, Education mental health and other socially acquired
traits. Finally, Cultural Capital includes values, beliefs, dispositions, perceptions and attributes
that emanate from membership in a particular group (Bourdieu, 1984).
Taken together, these attributes and their interaction in Recovery Capital Theory are a
way to more specifically understand substance use disorder recovery in the context of Social
Capital theory. Drug courts can assist with the acquisition of Recovery Capital in the same ways
as described for Social Capital theory above. A way to conceptualize Recovery Capital in the
context of drug courts is to think of the drug court participants as building Social Capital that can
in turn foster recovery capital (Neale & Stevenson, 2015). Cloud & Granfield (2008) point out
that, ironically, access to the kinds of resources that constitute Recovery Capital are the very
resources that would allow individuals to access treatment and services prior to an admission to
drug court. Consequently, a drug court can often be a resource of last resort for those who via
life circumstance or via substance abuse have never gained (or lost previously held) Recovery
Capital.

35
Conceptual Model
The complex systems interacting with the individual are so open to numerous variables
that attempting to understand how to conceptualize the Life Course in understandable terms can
be a daunting task. Figure 2.1 simplifies Life Course Theory in such a way as to understand how
variables interact with each other to affect an individual’s life course, bending it towards or away
from certain behaviors and actions. Referring to the figure below, this study conceptualizes an
individual’s life course as straddling a line between adaptive, socially compliant behavior (the
top half of the figure) and maladaptive criminal behavior (the bottom half of the figure). The
downward arrow on the top represents factors that may push individuals towards lower,
maladaptive side and the upward arrow represents factors that would influence a life course
towards social connectedness and abstinence. This study’s premise holds that factors in the
upward arrow are stressed and reinforced by drug courts and are an influence (or “encouraging a
turning point” in Life Course parlance) that would push an individual more towards socially
accepted behavior and reduce the influence of potentially negative influences and traits.
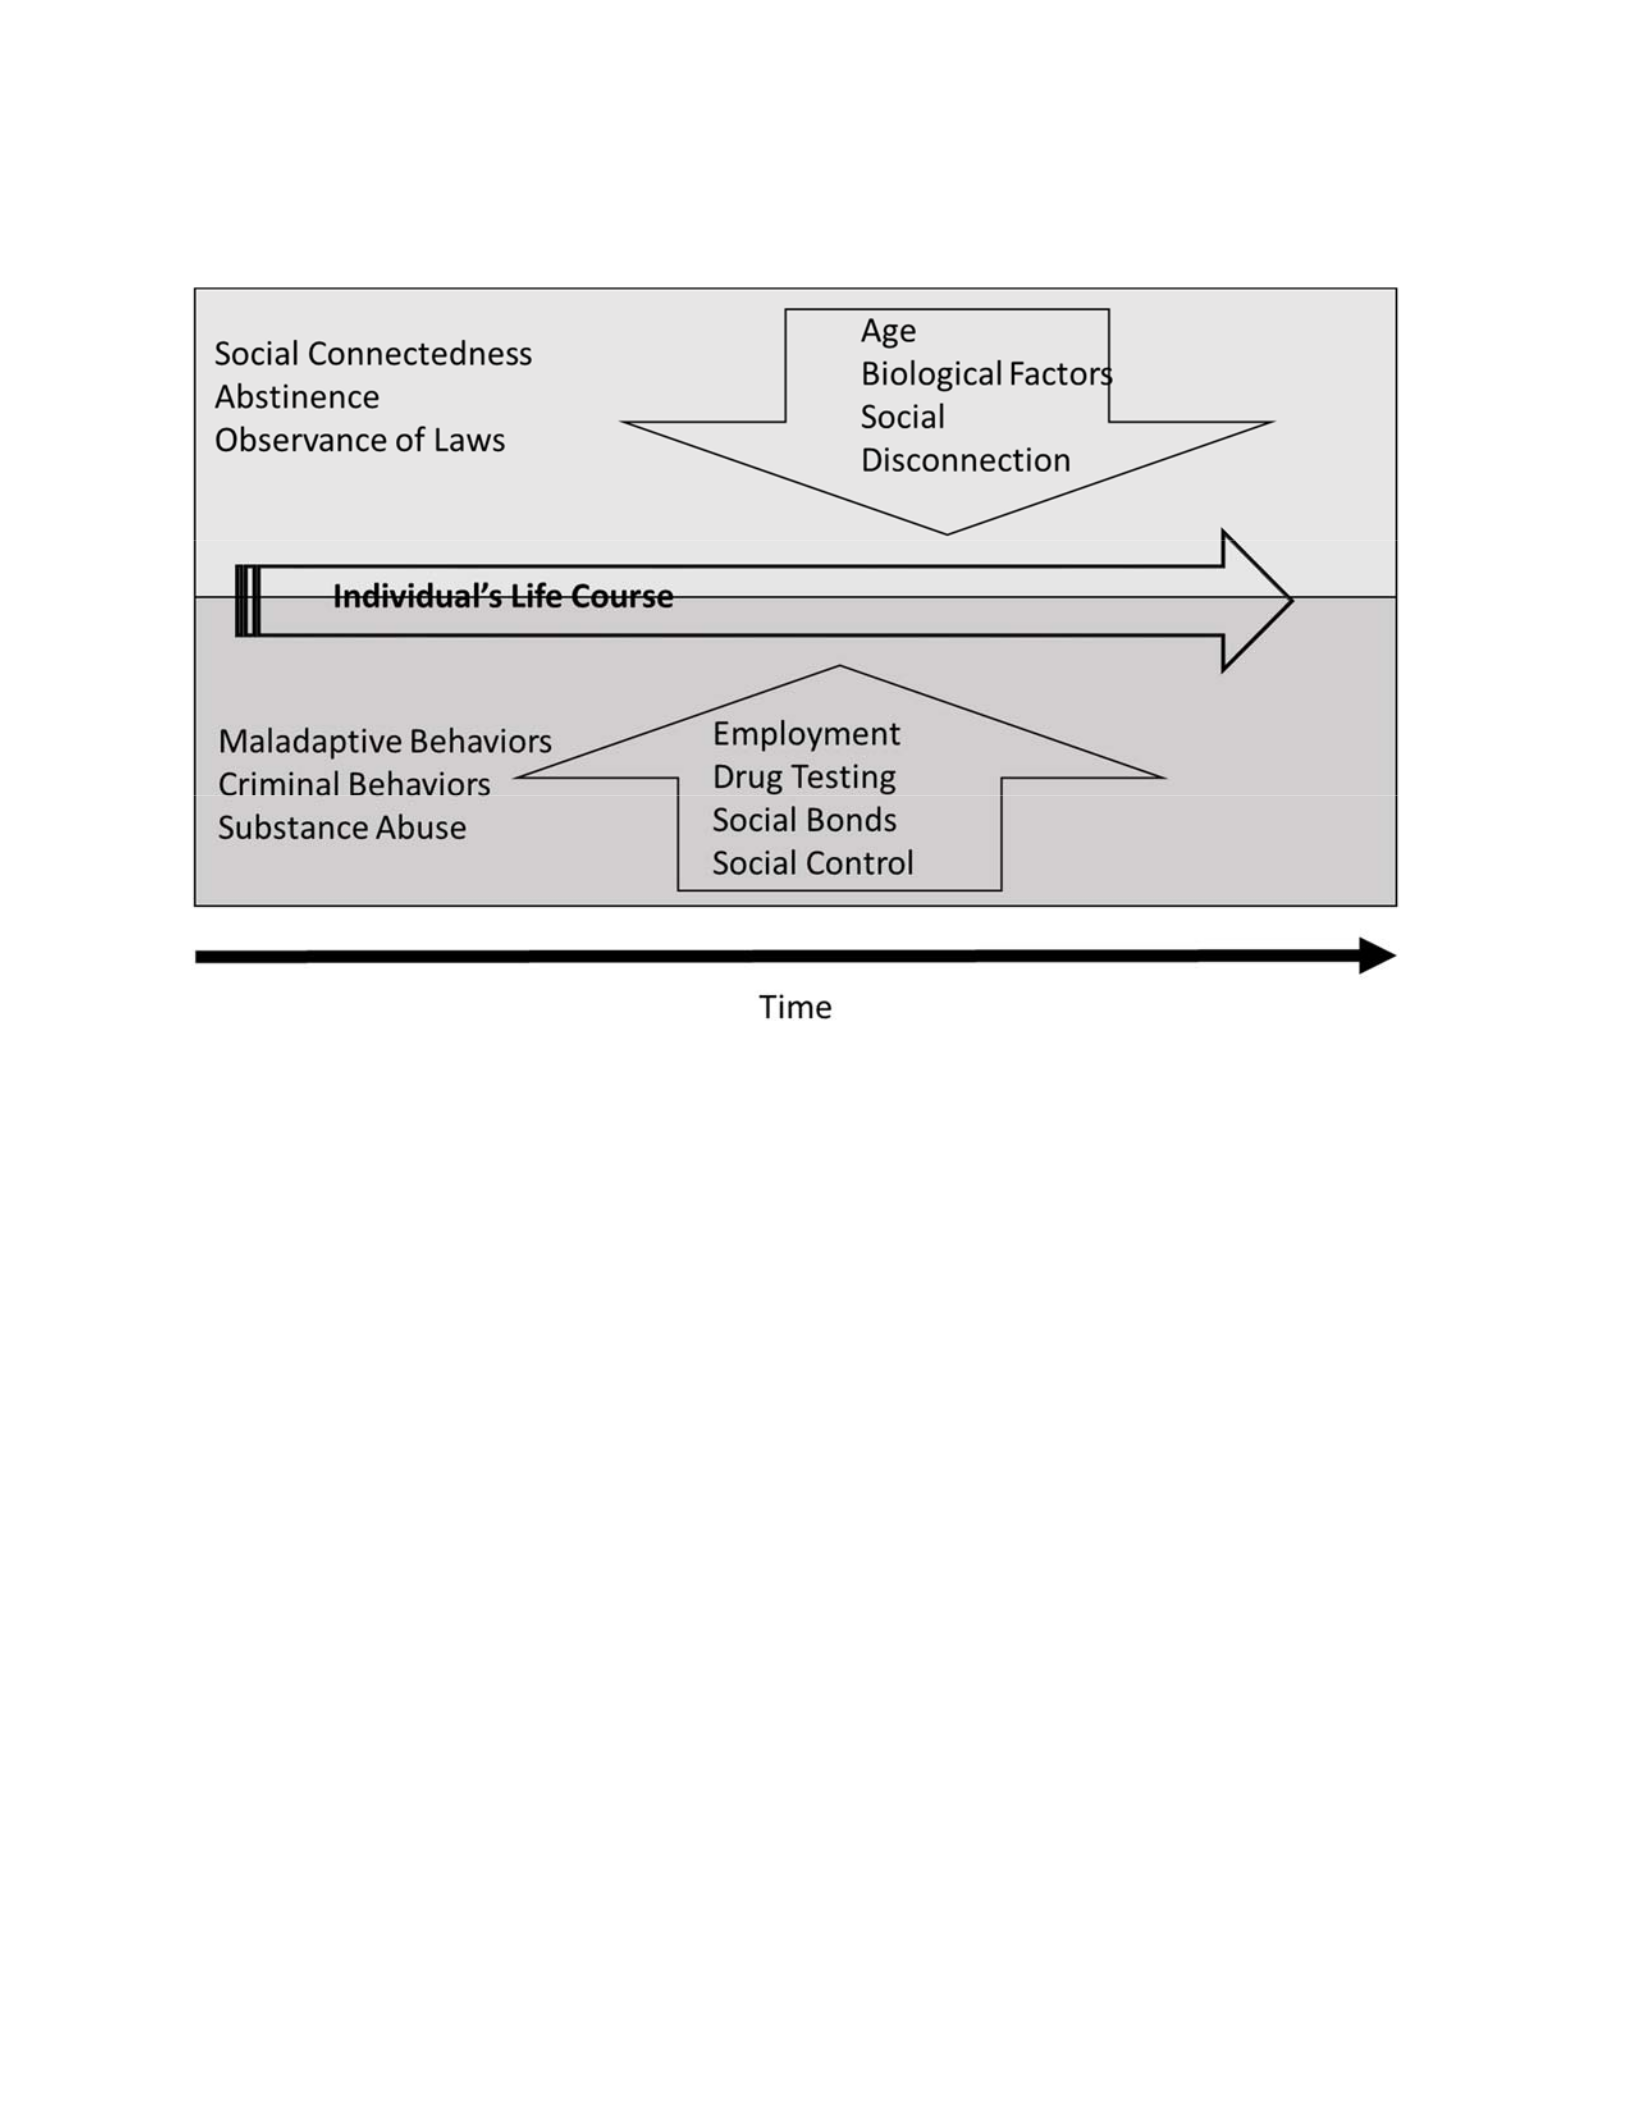
36
Figure 3.3 Conceptual Model
This model is a starting point for examining factors relating to drug court success. It is a
given that no one particular life is completely on either side of social connectedness or criminal
behavior—the model is more of a guideline for conceptualizing how factors influence moving in
and out of these realms than as an absolute understanding of the life course. The variables
selected in Chapter Three of this study reflect the thinking behind this model.

37
Conclusion
While drug courts have been subject to much scrutiny in terms of efficacy, much of the
literature (and virtually no literature in social work) fails to provide a coherent, theoretical
framework for how to understand them. By applying a Life Course Perspective and layering that
with an understanding of drug courts as builders of social and recovery capital, we can begin to
winnow down elements that appear to be major influencers on the success of drug court
participants. By building the knowledge base in this way, the proven results and cost
effectiveness of drug courts can be coupled with an evidence-based and theoretically grounded
approach. Chapter three expands upon the theoretical base by isolating factors to be studied in
drug courts and making an attempt to statistically link those factors with drug court graduation.

38
Chapter 3: Methodology
The goal of this research project is 1) to contribute to the general knowledge base of drug
courts by identifying factors that contribute to success in drug court programs, 2) statistically test
factors that are supported by theory and the literature as potential contributors to success in drug
court programs, and 3) examine the drug court experience at different time points to find if there
are potential risk and protective factors that may aid drug court professionals in identifying areas
upon which they should focus their efforts during the course of drug court treatment and
services. The overarching research question of this study is: What factors contribute to success
(as defined by graduation) in a drug court program?
To attempt to answer these questions, 3 analyses will be performed:
1. What is the impact of race, gender, age, abstinence from drug use, employment, housing
stability, having children, attendance at self-help group days, and educational level
(measured at intake) on graduation?
2. What is the impact of race, gender, age, abstinence from drug use, employment, housing
stability, having children, attendance at self-help group days and educational level
(measured at intake) on presence in the drug court program until the six-month mark?
3. What is the impact of race, gender, age, abstinence from drug use, employment, housing
stability, having children, attendance at self-help group days, and educational level
(measured at the six-month time point) on graduation?
While these questions look at identical factors, the different time points for questions one and
two will allow for an assessment that goes to screening of drug court participants and warning
signs to look for as potential stumbling blocks for participants. In question one, the dependent
variable of graduation will allow the study to tease out potential factors to look for prior to the

39
drug court intervention which may assist in screening for good candidates with a high probability
of success and help identify candidates that may need additional services to optimize chances for
graduation. Question 2 with the dependent variable of making it to the six-month mark asks a
similar, but more specific question as to factors leading to retention (a prerequisite to graduation)
in the program. Finally, Question 3 is one which will shed the most light on the intervention
itself. Question 3 is at a point where the vast majority of participants have secured employment
(as required by the RADTC) and a point where they are fully invested in the program and are
likely to be receiving the full spectrum of services. By assessing factors at the six-month point in
the program with graduation as the dependent variable, this question is the most germane with
regard to impact of the program services themselves.
The GPRA Instrument
The Government Performance and Results Act (GPRA) is the legislative framework that
requires federally funded programs to define and report performance objectives (Darby &
Kinnevy, 2010). At its foundation, GPRA was an effort in the early years of the Clinton
Administration in attempting to streamline and make government programs more accountable to
taxpayers. The premise was taken from Osborne & Graebler’s (1992) Reinventing Government
(Darby & Kinnevy, 2010; Osborne, 1993). The notion behind the act was to create quantitative
and systematic data gathering allowing for an improvement in program outcomes and
measurable program benchmarks allowing for more efficient use of government funding.
Numerous government agencies were required to develop measures to comply with the GPRA
legislation. Groups formed under SAMHSA’s direction identified demographic information and
five co-occurring treatment domains to be measured and reported to congress. The result of this

40
effort was the CSAT GPRA Client Outcome Measures for Discretionary Programs (referred to as
the GPRA Instrument in this study). The GPRA Instrument is attached as Appendix 2 of this
study.
The site of this study (RADTC) was the recipient of a targeted capacity expansion grant
for their drug court site. As a requirement of the grant, the GPRA Instrument was required to be
administered to all drug court participants receiving services under the grant. The instrument is a
structured interview consisting of approximately 200 questions that, as a requirement for grant
funding, was given at several time points: intake, six months, twelve months and upon discharge
from the program. The interviews were conducted by drug court clinical staff and others under
their supervision. Participation in the GPRA Instrument evaluation was completely voluntary
and all participants were required by SAMHSA and the program to review and sign informed
consents prior to participating. The participants were informed of their right to withdraw from
the evaluation at any point and all interviews were kept strictly confidential. In keeping with the
ethical requirements for use of this data, the next section of this study briefly outlines Human
Subjects Protection for this study.
Data Set
The data set being utilized for this study will be retrieved from the Services
Accountability Improvement System (SAIS). Once the GPRA Instrument is administered to
participants, it is then entered by program staff into the SAIS online system. While the
instrument does contain demographic information such as age, race and gender, there is no
directly identifiable information collected. No names were captured and no readily available
identifiers such as social security numbers are used (a randomly assigned study ID is used to

41
match cases). In addition, the subjects involved in this study gave informed consent at the time
of interview and were continually offered the option to withdraw. Further, all subjects for whom
data will be used have since graduated or otherwise separated from the RADTC program so there
is no way in which use of this data could affect their progress in the program. Taking into
account the fact that data is de-identified with the fact that, at a minimum, all program
participants have been separated from the program for a minimum of two years, it is anticipated
that use of this data will cause no harm to those whose data is being utilized. With the preceding
facts in mind, this project was deemed “No IRB Necessary” by the VCU School of Social Work.
Data for this study was collected starting in March of 2011 with the last interview being
conducted in October of 2013. The total n=209 counting all of the interviews ranging from
intake to discharge. The breakdown by interview type is as follows:
● Intake Interviews n=128
● Six Month Follow Up n=73
● Discharge Interview n=8
The data set consists of over 225 variables corresponding to the answers in the GPRA
Instrument. The variables used for this study have been selected based upon grounding in the
theories discussed in Chapter 2 and upon a review of the literature. A breakdown of the
variables for each research question of this study is illustrated in Table 3.1 below.
Secondary Data Analysis
The present study design employs quantitative data methods in a correlational design that
attempts to test if relationships suggested by theory occur (Drake & Jonson-Reid, 2008). The
study utilizes objective measures using statistical controls to test the association of multiple

42
variables to outcomes. By utilizing secondary data, this study is able to cover a period of time in
a lengthy drug court process (as much as two years in some cases) that may not normally be
possible for a dissertation. A common criticism of use of secondary data is that there may be
information or questions that would ideally be asked in primary data collection that are not
available in the secondary data source. However, this author has attempted to ground the
exploration in theory and previous drug court study in a way that makes the available data
relevant, useful and viable. Vartanian (2010) argues that “in many ways, users of secondary data
trade control over the conditions and quality of the data collection for accessibility, convenience
and reduced costs in time, money and inconvenience to the participants” (p 16).
While secondary data is most often associated with large-scale, national data sets, in this
case the secondary data allows this author to avoid costs and time investment that would make
this research project impossible if only able to use primary sources. Sample sizes are usually
larger for secondary data sources, this is not always the case (Vartanian, 2010). When looking at
specific subpopulations (in this case the universe of individuals in drug court), there is not a
readily available large data set ready for use. Consequently, secondary data in the case of this
study helps to shed light on a smaller group of individuals and follow them longitudinally using
evaluation data collected for other purposes. Secondary data may also subvert the process by
“driving the question” or only creating questions that can be answered by the available data
(Vartanian, 2010). This leaves this researcher, in this case, with a cost/benefit analysis to make
in terms of use of secondary data. The ability to view a population of interest over time in a
unique setting is what made use of secondary data for the present study useful and enlightening.
The value of data collected by SAMHSA for the purposes of governmental reporting can
shed light on an important, emerging trend in criminal justice. This author has judged that use of

43
secondary data in this study can help to answer important questions on aspects which lead to
drug court success. The limitations in the use of secondary data will be addressed by use of
statistical controls that will quantify relationships between multiple variables and demonstrate
whether or not sample sizes available are sufficient to demonstrate those relationships. As time
goes on, it is possible that secondary data sources for drug court will grow, but as of this writing
these limitations, not uncommon in the social sciences, must be acknowledged as existing in real
world situations.
Data Analysis Plan
Variables
The dependent variable for research questions one and three of this study is graduation
from the drug court program. Graduation is an output measure simply defined as successful
completion of the drug court program and is a dichotomous variable of yes or no (see Chapter 5
for a discussion of graduation as an outcome). For question 2, the dependent variable is also
dichotomous yes or no as to whether the participant was still in the program (retention proxy) at
the six-month mark of the program. Consequently, the nature of the study will purposively
assign drug court participants into groups for each question (Graduated and Not Graduated for
Research Questions 1 and 3 and Enrolled and Not Enrolled at Six Months for Question 2).
The independent variables are the same for each question. Table 3.1 below outlines the
breakdown of the research questions along with variables matrix.
44
Table 3.1 Research Questions and Variable Matrix
Overarching
Research Question
Dependent
Variables
Independent
Variables
Variable Name
RQ1: What is the
impact of race,
gender, age,
abstinence from drug
use, employment,
housing stability,
having children,
attendance at self-
help group days and
education level at
intake on graduation?
Graduation Race
Gender
Age
Abstinence
Employment
Housing Stability
Children
Self-Help Group
Attendance Days
Education Level
Graduation-
Dichotomous Yes/No
1: Race
2: Gender
3: Age
4: Abstinence
5: Employment
6: Housing Stability
7: Children
8: Self-Help Group
Attendance Days
9: Education Level
RQ2: What is the
impact of race,
gender, age,
abstinence from drug
use, employment,
housing stability,
having children,
attendance at self-
help group days and
education level on
remaining in the drug
court program until
the six month mark?
Enrolled at Six
Months
Race
Gender
Age
Abstinence
Employment
Housing Stability
Children
Self-Help Group
Attendance Days
Education Level
Graduation-
Dichotomous Yes/No
1: Race
2: Gender
3: Age
4: Abstinence
5: Employment
6: Housing Stability
7: Children
8: Self-Help Group
Attendance Days
9: Education Level
45
RQ3: What is the
impact of race,
gender, age,
abstinence from drug
use, employment,
housing stability,
having children,
attendance at self-
help group days and
education at the six
month time point on
graduation?
GraduationRace
Gender
Age
Abstinence
Employment
Housing Stability
Children
Self-Help Group
Attendance Days
Education
Graduation-
Dichotomous Yes/No
1: Race
2: Gender
3: Age
4: Abstinence
5: Employment
6: Housing Stability
7: Children
8: Self-Help Group
Attendance Days
9: Education
The analysis will consist of a discriminant function analysis (DFA). Discriminant
function analysis is used to determine which continuous variables discriminate between two or
more naturally occurring groups (Poulson & French, 2008). The primary usefulness of DFA is
to determine whether or not the combination of predictors can reliably predict group membership
(Tabachnick & Fidell, 2013). DFA also provides the ability to analyze the complexity of the
variables and the interrelatedness of the variables simultaneously (Dattalo, 1995). DFA
automatically determines some optimal combination of variables so that the first function
provides the most overall discrimination between groups, the second provides second most, and
so on (Poulsen & French, 2008). The ability to examine these multiple variables in one analysis
is another reason the DFA is appropriate for this study. Logistic regression was considered as a
possible analysis for this study, however, the more demanding nature with regard to N make
DFA a more useful procedure with this particular data set. Consequently, DFA was determined
to be the most appropriate statistical procedure for use with this data set.

46
Conclusion
The purpose of this study is to identify factors leading to success in drug court programs.
Knowledge of how the influence of the key components of drug court coupled with inherent
demographic traits participants impacts success is addressed, but not nearly in enough depth in
the extant literature. Grounding in theory, while present in scattered studies, takes a back seat to
analysis of policy and overall general analysis of drug court impact. By examining selected
aspects of the drug court intervention and participants, the expectation of this study is to arrive at
success factors that can be further focused in future research in this and other drug courts to
arrive at more generalizable conclusions. By gaining this knowledge, this author hopes to
contribute understanding of factors influencing success in drug court in a way that will address a
massive societal problem and better serve the needs of drug court participants.

47
Chapter 4: Results
Introduction:
This study focused on the impact of various demographic attributes of drug court
participants along with some elements common to drug courts and assessed the impact of these
variables on graduation from drug court. As a secondary question, the impact of these
demographic attributes and drug court program elements were assessed to gauge their impact on
remaining in a drug court program. The questions examined for this study are:
1. What is the impact of race, gender, age, abstinence from drug use, employment, housing
stability, having children, attendance at self-help group days, and educational level
(measured at intake) on graduation?
2. What is the impact of race, gender, age, abstinence from drug use, employment, housing
stability, having children, attendance at self-help group days and educational level
(measured at intake) on presence in the drug court program until the six-month mark?
3. What is the impact of race, gender, age, abstinence from drug use, employment, housing
stability, having children, attendance at self-help group days, and educational level
(measured at the six-month time point) on graduation?
Prescreening Data
Prior to data analysis, this data set was prescreened for the following factors: absence of
data errors; data completeness; absence of multicolinearity; multivariate normality; absence of
outliers; linearity; and homoscedasticity.

48
Data Completeness. This data was prescreened for missing values in the Statistical
Package for the Social Sciences (SPSS) 23. Data was recoded with missing data coded as 1 and
all other values coded as 0. The three identified categories for missing data are missing
completely at random (MCAR), missing at random (MAR) and missing not at random (MNAR)
(Little & Rubin, 2014) . In this particular data set, missing data can most likely be attributed to
keying errors by drug court staff and/or incorrect completion of the GPRA interview by drug
court staff.
In this study, a bivariate correlation was produced to assess missing data. The matrix
produced a Pearson’s r value of less than .05 in all cases except for the variables of 30 Day
Abstinence and Children. These two variables had a perfect correlation for missing data. Both
of these variables had 1 case of missing data each. Other than the possibility of keying errors
and/or errors in conduction of the interview, no particular reason for this correlation was
immediately evident. In this case, it was determined that a missing data substitution was not
appropriate in this situation (P Dattalo, personal communication, July 11, 2016). Consequently,
the correlation analysis suggests this data set should be defined as missing not at random
(MNAR).
Outliers. Data was also screened for outliers using the Cook’s distance measure D
(Cook’s D) in order to detect the impact of outliers in this data set. Cook's distance addresses
the question: How much change will there be in the parameter estimates if a specific data point is
removed? Data points for which the answer is "a great deal of change" are said to be influential
(Lorenz, 1987). For this study, a Cook’s D screening was run on the models for all three
research questions. The Cook’s D cutoff for this study was determined by using the N of the
sample for each research question then dividing 4 by sample size.

49
Question 1: 4/128 = cutoff of .03125 (4 cases deleted)
Question 2: 4/128 = cutoff of .03125 (6 cases deleted)
Question 3: 4/73 = cutoff of .0548 (6 cases deleted).
Absence of multicolinearity. For this study, an examination of bivariate correlations
among independent variables for each research question was conducted. The results were as
follows:
Question 1: No Pearson’s r value was greater than .50 for any pair of IV’s
Question 2: No Pearson’s r value was greater than .50 for any pair of IV’s
Question 3: No Pearson’s r value was greater than .50 for any pair of IV’s
Homoscedasticity. Homoscedasticity is the assumption that the variability in scores for
one variable is equal at all values of another variable (Dattalo, 2013). Homoscedasticity can be
evaluated by examination of a plot of standardized predicted values as a function of standardized
residual values (Dattalo, 2013). For this study, plots of residuals versus predicted values were
reviewed to determine if residuals were a function of predicted values. A scatterplot, histogram
and p-plot were examined for each research question’s data sets.
For questions 1 and 2, the resultant analysis was that the data exhibits low
heteroscedasticity
For question 3, the figures demonstrated moderate heteroscedasticity
Most researchers consider DFA to be robust against moderate violations of this assumption.
The ideal is for an even distribution or a normal distribution depending on the graph (P. Dattalo,
personal communication, June 30, 2016). However, it should be noted that a violation of

50
homoscedasticity can make it difficult to estimate the standard error and usually results in
standard error estimates that are either too large or too small (Dattalo, 2013). While this must be
taken into account for the data analysis, the robustness of DFA to moderate violations were
deemed satisfactory to proceed.
Sample Size/Power Analysis
A power analysis was conducted in G Power (a widely used freeware power analysis
software) to determine minimally accepted sample sizes for this study. Power is the probability
of rejecting the null when a particular alternative hypothesis is true (Dattalo, 2008). Put simply,
a power analysis allows the researcher the confidence to determine if the representative sample
of a population being studied does actually represent that population. Due to a multivariate
analysis of variance (MANOVA) being mathematically equivalent to a DFA, an A priori
MANOVA: Global Effects analysis was used for the G Power calculation. The results of the
power analysis are summarized in Figure 4.1 below.
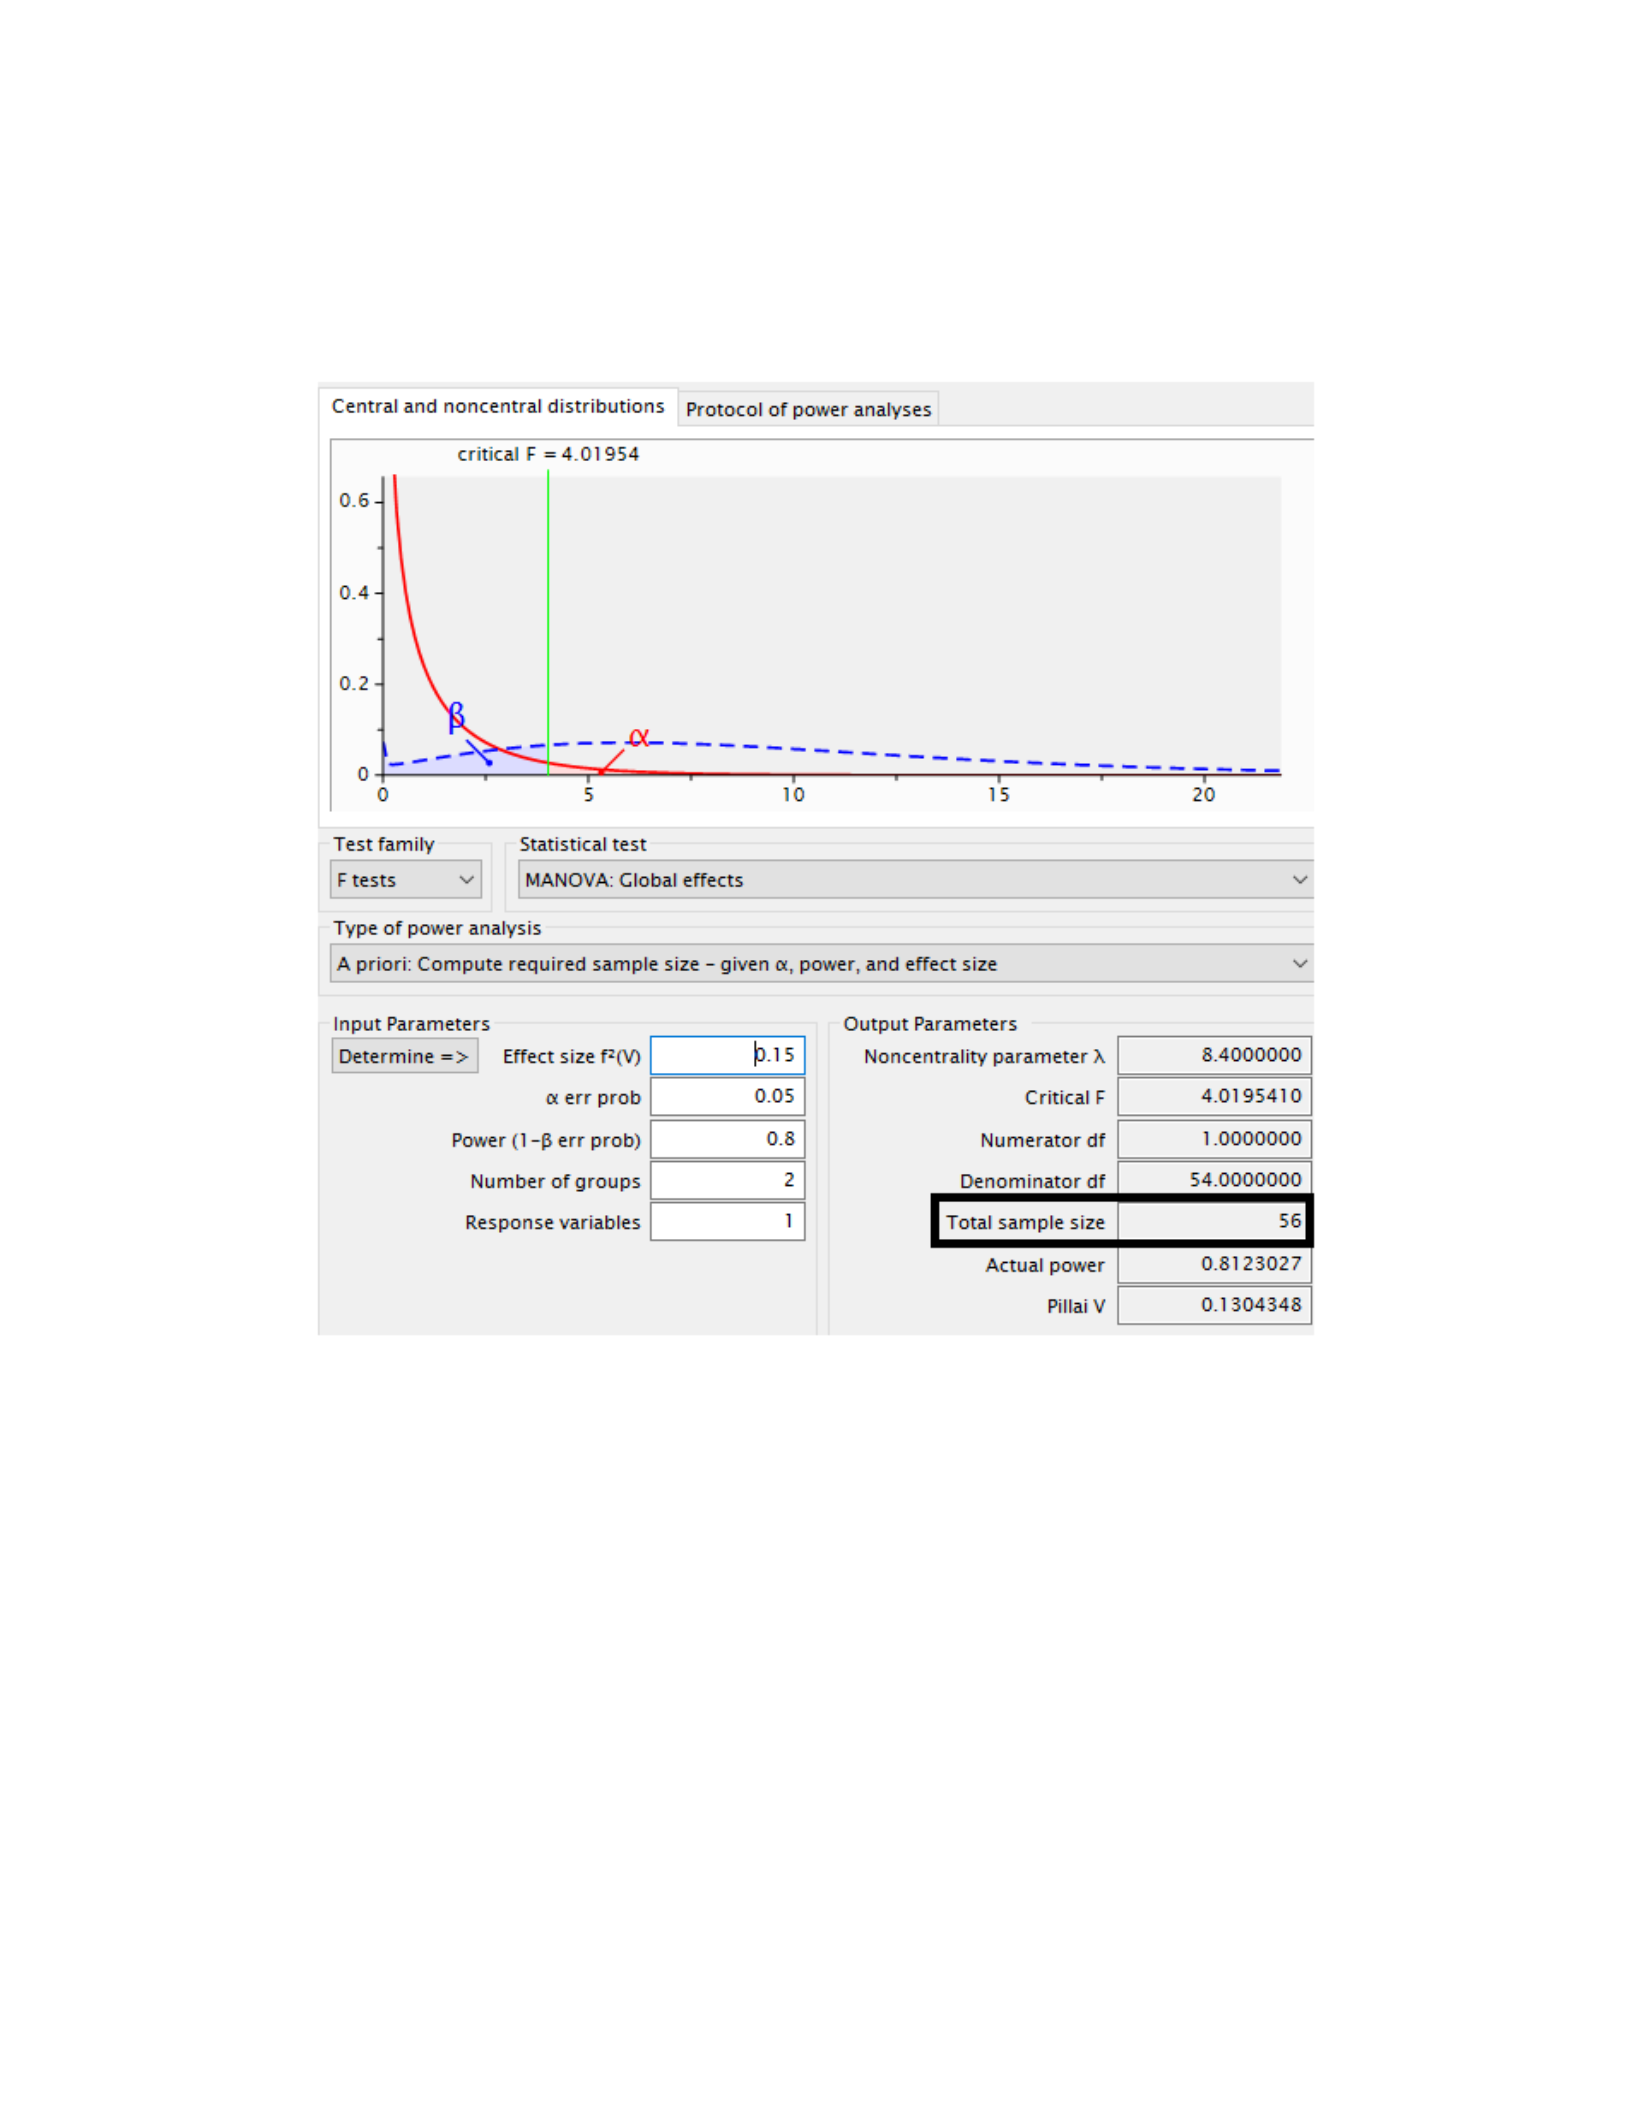
51
Figure 4.1 GPower Sample Power Analysis
Using a .15 effect size, an alpha of .05 and a power of .8 for the F tests G Power indicated that a
minimally acceptable sample size for this analysis was 56. The N of all three research questions
meets the minimum sample size criteria.
Results from the screening procedures and power analysis were not considered a major
barrier to proceeding with the discriminant function analysis (DFA), below.

52
DFA
Discriminant function analysis is used to determine which continuous variables
discriminate between two or more naturally occurring groups (Poulsen & French, 2008). DFA
answers the question: “can a combination of variables be used to predict group membership?”
Usually, several variables are included in a study to see which ones contribute to the
discrimination between groups (Poulsen & French, 2008). In the case of this study, the two
groups are divided among the one dependent variable (Graduated or Not Graduated in the case of
Questions 1 & 3 and Present in the Program at the 6 Month Mark or Not Present in the Program
at the 6 Month Mark in Question 2).
As with the data screening process, the data was analyzed in the Statistical Package for
the Social Sciences (SPSS) 23. Three different DFA models (each corresponding to the three
research question) were run to discriminate between 2 groups (as referenced in the preceding
paragraph. Box’s M was used to test the assumption that groups have equal variance-covariance
matrices (Dattalo, 1995).
Research question 1. The two group DFA was used to determine which variables
discriminate among the following groups: (1) graduated from the drug court program and (2) did
not graduate from the drug court program. The discriminating (independent) variables (taken at
intake) were age, gender, race, 30-day abstinence, days in self-help groups, stability in housing,
presence of children, educational level and employment status.
Box’s M was used to test the assumption (H0) of equality of variance-covariance
matrices. Box’s M equaled 58.450, F(2, 40237) = 1.18, p =0.182, which meets the assumption
of equality of variance-covariance matrices. The two group DFA yielded 1 discriminant

53
function. This discriminant function had a canonical correlation of .493. Wilk’s Lambda
equaled .756, Chi square (9, N= 113) 29.722, p <.001. Therefore, the H0 of no differences
among the group centroids is rejected.
Overall, approximately 69% of the original grouped cases were correctly classified. For
the graduated group, approximately 64% were correctly classified. For the not graduated group
approximately 25% were correctly classified.
Standardized coefficients were used to compare a variable’s relative relationship to a
function. These coefficients are summarized by function in Table 4.1. In terms of absolute size,
for function one, the presence of children was most important, followed by employment status
and 30-day abstinence.
Structure coefficients were also used to compare a variables relationship to a function and
are summarized in Table 4.2. For this question, these coefficients are generally consistent with
the standard coefficients.
Standardized discriminating coefficients quantify the relationship between a particular
discriminating variable and the discriminating function, while controlling for the effects of other
discriminating variables. Structure coefficients quantify the relationship between a
discriminating variable and the discriminating function. In other words, structure coefficients are
bivariate, zero-order coefficients; standardized discriminating coefficients are standardized,
partial coefficients (P Dattalo, personal communication, July 11, 2016). Consequently, there
may be an interaction between variables or another variable that is not accounted for in this
model.

54
In summary, the model for research question 1 demonstrated a low to moderate ability to
predict group membership with presence of children, employment and 30-day abstinence as the
most important discriminating variables. However, the function appears to have a moderate to
low utility based on the canonical r of .493
Research question 2. The two group DFA was used to determine which variables discriminate
among the following groups: (1) present in the program at the six-month mark and (2) not
present at the program at the six-month mark. The discriminating (independent) variables (taken
at intake) were age, gender, race, 30-day abstinence, days in self-help groups, stability in
housing, presence of children, educational level and employment status.
The Box’s M analysis returned an error stating that no test can be performed with fewer
than two nonsingular group covariance matrices (indicating nonsingularity). As this test is used
to test the assumption (H0) of equality of variance-covariance matrices, no equality of variance-
covariance matrices can be assumed for this model. This is likely due to the fact that, at the six-
month point, abstinence, presence at six months and employment have less variability across the
groups, not allowing the variance assumed for this statistical procedure. The two group DFA
yielded 1 discriminant function. This discriminant function had a canonical correlation of .495.
Wilk’s Lambda equaled .755, Chi square (9, N= 111) 29.349, p =.001. Therefore, the H0 of no
differences among the group centroids is rejected.
Overall, approximately 78% of the original grouped cases were correctly classified. For
the present at six-month group, approximately 75% were correctly classified. For the not present
at six-month group approximately 8% were correctly classified.

55
Standardized coefficients were used to compare a variables relative relationship to a
function. These coefficients are summarized by function in Table 4.1. In terms of absolute size,
for function one age was most important, followed by race and 30-day abstinence.
Structure coefficients were also used to compare a variables relationship to a function and
are summarized in table 4.2. For this question, race was the most important with 30-day
abstinence and education level being the next 2 highest effect sizes. As stated above, the
differences between the standardized and structure coefficients may be due to interaction or
factors not accounted for in the model.
In summary, the model for research question 2 demonstrated a low to moderate ability to
predict group membership with age, race and 30-day abstinence as the most important
discriminating variables. As with the previous model, the function appears to have a moderate to
low utility based on the canonical r of .495
Research question 3. The two group DFA was used to determine which variables
discriminate among the following groups: (1) graduation from the program and (2) not graduated
from the program. The discriminating (independent) variables (this time measured at the six-
month time point) were age, gender, race, 30-day abstinence, days in self-help groups, stability
in housing, presence of children, educational level and employment status.
As with research question 2, the Box’s M analysis returned an error stating that no test
can be performed with fewer than two nonsingular group covariance matrices. As this test is
used to test the assumption (H0) of equality of variance-covariance matrices, no equality of
variance-covariance matrices can be assumed for this model. Much like question 2, this question
also investigates effects of the independent variable at the six-month point. Also similar to
question 2 (due to program requirements) abstinence, graduation rates and employment have less

56
variability across the groups, not allowing the variance assumed for this statistical procedure.
The two group DFA yielded 1 discriminant function. This discriminant function had a canonical
correlation of .576. Wilk’s Lambda equaled .668, Chi square (9, N= 59) 21.146, p =.012.
Therefore, the H0 of no differences among the group centroids is rejected.
Overall, approximately 78% of the original grouped cases were correctly classified. For
the present at six-month group, approximately 75% were correctly classified. For the not present
at six-month group approximately 9% were correctly classified.
Standardized coefficients were used to compare a variables relative relationship to a
function. These coefficients are summarized by function in Table 4.1. In terms of absolute size,
for function one race was most important, followed by self-help group days and presence of
children.
Structure coefficients were also used to compare a variables relationship to a function and
are summarized in table 4.2. For this question, race was the most important with 30-day
abstinence and self-help group days being the next 2 highest effect sizes.
In summary, the model for research question 3 demonstrated a low to moderate ability to
predict group membership with race, self-help group days and presence of children as the most
important discriminating variables. The function appears to have a low utility based on the
canonical r of .576.

57
Table 4.1
DFA Standardized Coefficients
Standardized Coefficients Summary of the Three Models
Model 1 Model 2 Model 3
Children 0.635 -0.328 0.274
Employment Status 0.409 -0.459 -0.493
Race -0.404 0.600 0.778
Education Level -0.222 0.270 -0.175
30 Day Abstinence 0.360 0.425 -0.614
Age -0.572 0.695 0.186
Gender 0.028 -0.023 -0.212
Stability in Housing 0.076 0.239 0.013
Self-Help Group
Days
0.252 0.001 0.368
Rc 0.493 0.495 0.576
Wilk/s 0.756 0.755 0.668
Table 4.2:
Structure Coefficients Summary of the Three Models
Model 1 Model 2 Model 3
Children 0.531 -0.475 0.031
Employment Status 0.454 -0.435 -0.400
Race -0.447 0.490 0.565
Education Level -0.336 0.328 0.175
30 Day Abstinence 0.246 0.205 -0.356
Age -0.215 0.223 0.113
Gender 0.201 -0.112 -0.056
Stability in Housing 0.102 0.072 0.037
Self-Help Group
Days
-0.013 0.072 0.362
Rc 0.493 0.495 0.576

58
DFA
Structure Coefficients
Wilk’s 0.756 0.755 0.668

59
Table 4.3:
Variable Detail for Models 1 through 3
Variable Details for Models 1 through 3
Model
1
Model
2
Model
3
Graduated (present at 6 months for model 2)
Yes 51.60% 80.30% 66.20%
No 48.40% 19.70% 33.80%
Gender
Male 56.50% 55.70% 53.70%
Female 43.50% 44.30% 46.30%
Race
African-American 78.20% 77.90% 73.10%
White 21.80% 22.10% 26.90%
Mean Age 38.23 38.13 38.8
Median Age 39 39 40
Self Help Group Days Mean 11.65 11.88 13.5
Self Help Group Days Median 12 12 12
30 Day Abstinence
Yes 76.40% 78.50% 95.50%
No 23.60% 21.50% 4.50%
Children
Yes 69.90% 68.60% 68.70%
No 30.10% 31.40% 31.30%
Employment
Employed Full Time 1.60% 31.10% 62.70%
Employed Part Time 30.60% 7.40% 3.00%
Unemployed, Looking For Work 44.40% 43.40% 13.40%
Unemployed, Disabled 12.10% 11.50% 16.40%
Unemployed, Volunteer Work 0.80% 0.80% 0%
Unemployed, Not Looking For Work 3.20% 4.10% 3.00%
Education Level
Less Than High School 45.20% 45.10% 40.30%
HS Diploma or GED 31.50% 31.10% 40.30%
Technical School 4% 3.30% 3%
Some College 16.90% 18% 13.40%
Completed College or Higher 2.40% 2.50% 3%
Housing Situation
Own/Rent Apartment or Home 30.10% 29.80% 40.30%
Someone Else's Home 31.70% 31.40% 38.80%
Halfway House 2.40% 2.50% 7.50%
Residentail Treatment 16.30% 16.50% 6%
Homeless/Shelter 17.10% 16.50% 6%
Other 1.60% 2.50% 1.50%
N 113 111 59

60
Chapter 5: Discussion
Drug courts have been the subject of numerous studies that attempt to isolate their
effectiveness, effects on recidivism, internal workings and their various isolated elements.
Unfortunately, a small percentage of those studies are theory driven and/or comprehensive in
scope. For more than a decade, researchers have characterized drug courts as a ‘Black Box’
(Bouffard & Taxman, 2004; Goldkamp, White, & Robinson, 2001; Shaffer, 2011) that they have
portrayed as a mysterious process that eluded understanding. Drug courts have been accepted as
a fact of life in jurisdictions throughout the nation (and the world) as a ‘better’ solution than
traditional parole, probation and incarceration. Through the establishment of drug courts judges
in the U.S. have been the leaders primarily responsible for initiating the major shift in criminal
justice policy and practice regarding drug offenders (Cooper, 2015). There has not been a slow
methodical rollout of these courts via legislation or public outcry. Drug court expansion has
been the result of the efforts of individuals on the ‘front lines’ of criminal justice as a reaction to
a widespread feeling among many in the courts and law enforcement that the revolving door of
drug arrests and incarceration had to, somehow, be interrupted.
The ballooning body of research on drug courts has grown to the point where the
majority of literature endorses the effectiveness of drug courts, but not nearly enough researchers
attempt to ask ‘why’ they work or ‘how’ they work. Because drug courts, as an intervention, can
vary widely from jurisdiction to jurisdiction, this author would argue that there is a significant
‘treatment fidelity’ issue that bars fully understanding the phenomenon of drug courts as an
overall intervention. The increasing popularity of drug courts would seem to indicate that they
are here to stay. Policymakers on the local, state and national level as well as social workers

61
would do well to continue to expand the growing knowledge base regarding what ‘makes drug
courts tick’ and to be able to point to well-reasoned, theory-based explanations for their success.
This study was conducted to attempt to gain an understanding, through the lens of theory
and empirical support what inherent individual aspects of an individual and what major aspects
of the drug court intervention contribute to success (defined as graduation for the purposes of
this project) from drug court. In addition, a secondary question asking how longevity in drug
court (presence in the program at the six-month point) may be influenced by the same factors
studied for influence on graduation. This researcher has attempted to make this project unique
by viewing the journey of an individual in drug court through the lens of several theories. These
theories are commonly used in social work, criminal justice and substance use disorder research,
but combined take a combination of micro and macro approaches that are unique to social work
and not explored in depth in the extant literature.
This chapter begins with an examination of the limitations of the data and an examination
of the study findings. Next, this chapter contains a discussion of the implications of these
findings for social work and social justice and a discussion of the implications for social work
education. Lastly, this chapter ends with directions for future research.

62
Interpretation of the Data
Limitations of the Data
Graduation as Outcome. Drug court graduation is an outcome upon which there is
general agreement in the literature. However, it must be acknowledged that the programs and
requirements that lead to graduation from any particular drug court graduation may be different
from court to court. To accept that drug court graduation can be measured as an outcome, one
must peer inside the ‘Black Box’ and come to an understanding of what graduation is a proxy for
across drug courts. Going back to the key principals of drug court outlined above, this researcher
would argue that there are several items that can be universally agreed upon as part of a set of
outcomes that lead to graduation. Among the items that graduation is proxy for are: long term
drug and alcohol abstinence (monitored via frequent, random testing); attainment of
employment; and some form of drug treatment intervention (ranging from self-help groups to
group and individual interventions). Drug courts have become institutionalized enough and drug
court training via national organizations is standardized enough to have led to graduation being a
representation of a few agreed upon elements (the scope and intensity of which it must be
acknowledged vary from place to place).
This study was conducted in the Richmond Adult Drug Treatment Court, the guidelines
for which are available for review in Appendix 1. However, it must be acknowledged that these
guidelines were developed by the judge, practitioners, Commonwealth’s Attorney and other
stakeholders in this local system. There is a well-worn statement among individuals working in
drug courts that “If you’ve seen one drug court, you’ve seen one drug court.”. This variation and
‘customization’ of drug courts as an intervention should be acknowledged, but this researcher

63
would argue that it is not an impediment to developing a global understanding of drug courts by
examining a single drug court (at least as a first step).
Limitations of the GPRA Instrument. The GPRA Instrument (attached as Appendix 2)
was designed as a reporting tool for federal drug court grantees to relay program information to
federal funders. The data collected is self-reported by drug court participants. Consequently,
some of the information collected is particularly sensitive in a drug court context. As a central
tenet of any drug court program being sobriety and abstinence, participants would very likely be
reluctant to report alcohol and/or drug use. While frequent testing can assist with verifying
claims of abstinence, the self-interest of participants who are self-reporting drug and alcohol use
must be acknowledged. Another limitation of self-report in the GPRA are the items regarding
attendance at self-help groups. Self-help group attendance in the RADTC are another required
element of the program. While every attempt is made to verify attendance, it is another area to
note where veracity of self-reporting clients and program requirements may bump up against
each other.
Another item of note in the reporting of the GPRA data is that collection is a stepwise
process involving completion of a paper interview instrument that is completed by drug court
staff and then entered into the CSAT online system where it was then retrieved by this
researcher. As with any data entry keying errors, missing data and human error are pitfalls of the
process. While SAMHSA provided extensive training resources to those managing GPRA data,
it is likely a certain amount of error may occur in even the best situations. This potential for
error (which can have significant impacts when dealing with smaller sample sizes) is one which
researchers should also acknowledge, but should not present a barrier to examination of that data.

64
Group Variability. As drug court participants advanced through the program, items like
attendance at self-help groups, employment, housing stability and 30-day abstinence tended to
become more similar between cases as program requirements influenced the participants. This
likely affected the DFA models ability to accurately distinguish between groups and impacted
the predictive ability of the statistical analysis. This lack of variability is likely inherent in the
design of this study due to the fact that only individuals sill engaged with the program are
administered the GPRA interview. As this was an analysis of secondary data (the pros and cons
of which are addressed in Chapter 3), this was a side effect of working with the data available to
this researcher.
Data Analysis
This study examined three different research questions utilizing discriminate function
analysis (DFA). The results of the data and the models created suggested a low to medium
ability of the models to predict group assignment based on the same group of independent
variables being analyzed for contribution to graduation (with one model (1) examining the
variables at intake and one model (3) examining the variables at the six-month time point). The
third model (2) examined the same set of independent variables at the six-month time point and
attempted to predict group assignment at the graduation time point. While the models presented
low to moderate predictive ability, there is data to suggest important factors in drug court
success.
Models 2 and 3 performed slightly better than Model 1 as evidenced by the Wilk’s
Lambda of the three models (Table 4.2). Models 2 and 3 both involve comparisons using data at
the six-month time point (for Model 2 a DV of presence in the program at six months and for
Model 3 an examination of the IVs at the six-month time point with graduation as DV). For

65
Model 3, one interpretation is that at the six-month time point, success in the program is much
more likely. That is, the vast majority of individuals have secured employment, attended
meetings and attended court hearings. However, children drop out of the largest effect sizes
when comparing the IV’s at intake to presence at six months (Model 2). Why presence of
children seems to influence graduation, but not presence in the program at six months is another
interesting question to study in the future. The contribution of children to the factors studied in
this project are addressed in more detail below.
It is also interesting to note that for Models 2 and 3, the single most contributory factors
for group assignment were age and race. This is an interesting finding in that race and age are
not a readily changeable status (like education, employment or group attendance). The impact of
race and age on success in drug court is discussed below in the Directions for Future Research
section. These findings are ones that bear additional inquiry in the future as it raises significant
questions with regard to social justice and the cultural/ethnic competency of drug courts.
Model 1
Influence of Presence of Children. The largest contributor to graduation in Model 1
was whether or not the drug court participant had children. In the conceptual model presented in
Chapter 2, this would be one of the items this researcher describes as social connectedness. This
was an interesting finding due to the fact that there is nothing in current literature discussing
having children as a predictor of success. There are studies that emphasize the fact that
participation in drug treatment court does lead to reunification of families that have been
separated due to a parent’s drug use and/or criminal history (Gifford, Eldred, Vernerey, & Sloan,
2014; Levine, 2012). This is obviously a desirable outcome for drug court participants and this

66
fact alone warrants further investigation of how drug courts impact the children of participants.
In addition, there have been findings that women have better substance abuse treatment
outcomes if they can regain custody of their children (Fischer, Geiger, & Hughes, 2007).
The notion of children being tied to success in drug court brings to the fore a type of drug
court not addressed in this study, the family drug treatment court. Family Drug Treatment
Courts are another form of specialized, problem solving courts. These courts provide the setting
for a collaborative effort by the court and all the participants in the child protection system to
come together in a non-adversarial setting to determine the individual treatment needs of
substance-abusing parents whose children are under the jurisdiction of the dependency court
(Edwards & Ray, 2005). This finding could suggest that add on services such as onsite
childcare, women’s focused interventions and the addition of family inclusive therapies may
contribute to the success of drug courts in the long run.
Employment Status. The second most influential factor in group assignment in Model 1
was employment status at intake. Consistent with the framework of Social Capital and Recovery
Capital, this would indicate that individuals who enter the program with some form of
employment start with a ‘leg up’ in terms of having some Social/Recovery Capital upon entering
the program. This has implications that should be considered by drug court professionals.
For those without employment at intake, every effort should be made to secure
employment for those individuals as early as possible. With employment being a key
requirement of the drug court program, this would seem obvious. However, this finding would
seem to indicate that those individuals without employment are at greater risk than those who are
employed at intake. By emphasizing employment opportunities, job training and resume
building as a top priority in the earliest stages of drug court, those individuals entering ‘at risk’

67
due to not being employed may enjoy more success in the program and be less likely to re-offend
or relapse (leading to failure to graduate).
Those already employed at intake appear to represent the ‘low hanging fruit’ for drug
court staff. What must be avoided is ‘selecting for success’ and making sure that drug court
participants are “met where they are” and have individualized treatment plans that prioritize
employment for those not employed at intake. A recent study by (Webster, Staton-Tindall,
Dickson, Wilson, & Leukefeld, 2014) supports this view in its findings that showed that those
who were on negative pre-baseline work trajectories assigned to individually tailored
employment interventions in drug court were more likely to enter the workforce.
30 Day Abstinence. At intake, 30-day abstinence has not been monitored by weekly
drug testing. At every other time point, abstinence and sobriety are ‘baked in’ to the program
using random drug testing. This author would argue based on the review of numerous drug
courts that abstinence is one of the single most (if not the most) emphasized and tracked aspect
during the participant’s entire time in drug court. While further research documenting drug court
sanctions would be needed to bear this out, it is inarguably central to all drug court programs. It
makes intuitive sense that abstinence is a large factor contributing to success, but documentation
of how drug courts handle the common substance use disorder symptom of relapse (discussed
below in the Directions for Future Research) is another item that would bear further
investigation. Specifically, more intensive scrutiny of abstinence history at intake versus
abstinence at other program time points would be an informative investigation.

68
Model 2
Age. There are a number of studies that point to age as a predictor of success in drug
courts (Butzin, Saum, & Scarpitti, 2002; Deschenes∗, Ireland, & Kleinpeter, 2009; Rempel et al.,
2003). However, this author was unable to locate studies that looked at influence of age at the
six-month time point. The evidence of this study and the extant literature do support the idea
that age is an influence on drug court success. A further understanding of this connection
(perhaps through qualitative study) might shed some additional light on why this factor is found
to be a common influence.
Race. Another worthwhile area of inquiry for drug courts would be to delve deeper into
demographic aspects that contribute to success (or lack thereof) in drug courts. There have been
research questions exploring the impact of factors like race (Dannerbeck, Harris, Sundet, &
Lloyd, 2006) and gender (Dannerbeck, Sundet, & Lloyd, 2002). Studies like these have
indicated differences of outcome between different groups in drug courts. Tackling this issue
would serve the dual purposes of better tailoring drug courts for diverse populations and the
inherent social justice issues that already plague the justice system such as the over
representation of minorities vis-à-vis the general population of the United States in jails and
prisons. In light of the findings of Models 2 and 3, this is an area of future study that should be a
priority for drug court researchers.
30 Day Abstinence. 30-day abstinence is discussed above with Model 1. However, the
reason why 30-day abstinence at intake would influence graduation and presence in the program
at 6 months but not significantly predict from the six-month time point (as in Model 3 below) is
not sufficiently addressed by this study. This would be another connection wherein additional
inquiry may address more completely

69
Model 3
Race. As discussed immediately above, this is a studied, but not understood factor in
drug court success. Understanding of race at any time point in the drug court process is a worthy
subject of study going forward.
Self-Help Group Attendance. Model 3 indicated a correlation between days attended at
self-help groups at the six-month time point with graduation. However, the number required in
phase one is not specified in the RADTC manual. These findings suggest that, for those not
already in the habit of attending groups, additional emphasis and perhaps additional meetings
may be warranted. The issue of what constitutes the necessary and sufficient ‘dosage’ of 12 step
and other self-help groups is one that the data suggest may be worth exploring. Most drug courts
(as with the RADTC after phase I and into aftercare) specify a number of self-help groups
participants should attend as part of their program. It is possible that these numbers can be
titrated for more at-risk participants to ‘even the playing field’ for those who enter the program
with additional resources that may impact their success in drug court.
Presence of Children. This influencing factor is discussed above, however, why
presence of children seems to influence graduation but not presence in the program at six months
is not fully addressed by this study design. Qualitative study and collection of more information
on the living situation of children of drug court participants (i.e.; are they living with the
participant, has there been a separation from parents by social services) are two ideas that may
make for an interesting study.

70
It should be noted that Model 3 is the strongest of the models examined. It suggests that
this six-month time period is an important one to study and that the relationships (particularly
with 12 step group days) should be a priority for future studies.
Implications for Social Work and Social Justice. Drug courts began as a unique
intervention to serve dual aims: to reduce the cost to the system of repeat drug offenders and to
merge treatment and judicial supervision in a way that improved the lives of those in the legal
system due mainly to substance use disorders. On its face, the second aim of providing treatment
instead of punishment for drug crimes is compatible with the aims of social justice and the
mission of social work. The idea of reducing costs and slowing the revolving door of
incarceration that were the status quo of drug crimes are a helpful policy byproduct that assists in
the proliferation of drug courts.
From a macro social work perspective, drug courts have been a policy intervention that
have served to foster social justice for the people who have avoided jail time and improved their
lives via participation in drug court programs. Social workers must be aware of the personal
agency of each individual participating in drug court and their right not to participate in drug
court. There have been Constitutional arguments with regard to due process in drug court
(Hoffman, 1999). The latitude judges are given in most drug courts may seem capricious and, in
some cases, could be abused. Drug courts have been described as “experimentalist” government
(Dorf & Sabel, 2000) and, as such, should not be accepted without empirical evidence of their
effectiveness and with an eye towards preserving the free will and inherent rights of those
participating. This author believes that the ongoing ‘laboratory’ of drug courts are a natural
place for social workers and social work values. The perspective and ethical code social workers

71
bring to the table in drug courts make us uniquely able to consider the larger policy implications
of drug court while serving our clients.
From a micro social work perspective, social workers have long been on the front lines of
treating individuals with substance use disorders. The courts system is another arena in which to
apply these skills. Further, an estimated one third of drug court participants have co-occurring
disorders (Peters, 2008). Clinical social worker’s training in the diagnoses of behavioral health
disorders are a natural fit for this setting. There is also a place for the practice of “forensic social
work”. If one considers social work in corrections and probation, forensic mental health,
substance abuse, family and criminal courts, domestic violence and child abuse and neglect,
juvenile justice, crime victims, and police social work, we would realize that many in the
profession are engaged in forensic social work (Roberts & Brownell, 1999). It is time for social
workers to embrace that role and develop it as way to merge micro and macro social work
practice while seeking social justice.
There is a strong social justice argument to be made for drug courts. They represent a
paradigm shift towards treatment of those with substance use disorders in the criminal justice
system. As our understanding of substance use disorders broadens, we see it for what it is, a
disease of the brain. No one would seriously argue that a patient who sees a doctor for an
infection should be punished if the first antibiotic prescribed does not cure the infection
(Lessenger & Roper, 2008). In much the same way, if we accept that substance use disorders are
a disease, punishment for relapse should not be as dire as immediate incarceration. Drug courts
must, as part of their mandate, punish behavioral infractions. However, most courts such as
RADTC distinguish between actions that are behavioral and actions related to addiction. In this

72
way, criminal and or maladaptive behaviors can be modified as well as the disease of addiction
treated.
There is additional work to be done with regard to drug courts on the social justice front.
Social workers must advocate to ‘push’ the treatment vs. punishment paradigm along to other
areas of society. For example, individuals who have been charged/convicted of felony drug
offenses will be denied (1) welfare benefits; (2) educational loans; (3) public housing; and (4) the
right to vote (Cooper, 2015). Employment opportunities are also hampered by required
disclosure of convictions and licensure and/or security clearance requirements that exclude
persons with a record involving drug offenses. Further, (Cooper, 2014) points out that
“deportation proceedings can be instituted – even for persons with legal immigration status --
based upon a drug charge, even one that was dismissed”.
These problem solving courts are a way to tackle an intractable and growing social
problem by trying something that is more strengths based, less punitive, more person centered
and recovery oriented. While there is an argument that there are issues of coercion involved in
drug courts, the argument should be more properly framed as an alternative to simply
warehousing those with substance use disorders in prison and jail. With all of this in mind, this
author would argue that drug courts are a natural fit for seeking social justice and for the ethical,
productive practice of social work.
Implications for Social Work Education.
As drug courts continue to expand social work educators would be well served to
emphasize the value of social work in criminal justice settings. Seeking and encouraging field
placements in the judiciary would benefit problem solving courts by bringing in more individuals

73
with the strengths based perspective that social workers bring. Additionally, educating and
employing more social workers can help bring a clinical rather than law enforcement or
parole/probation perspective to judicial supervision.
To promote effective social work practice, the curriculums of schools of social work
should reflect the changing face of the criminal justice population that include increased numbers
of individuals with co-occurring substance use disorders and mental illness by including content
on drug use, mental illness, and the consequences of these conditions on individuals within the
criminal justice system. It is also suggestive that social work students should receive additional
instruction on working with involuntary clients and their families to ensure they are competent to
address the needs of this population properly and with competence (Tyuse & Linhorst, 2005).
Directions for Future Research.
It would be difficult to find a judicial/substance use disorder phenomenon that has been
studied as much as drug courts have in the last two decades. However, there are several areas
ripe for further inquiry that would assist researchers in understanding the impact of these courts.
The understanding of what influences drug court outcomes would benefit greatly from
further qualitative inquiry. So much of the journey of individuals in drug court is a personal one.
The voice of those experiencing the program itself (Wolfer, 2006) would be an invaluable tool in
further theory development and in answering the question of ‘why’ drug courts work, not just the
question of ‘if’ they work. One major finding of qualitative studies done in drug courts has been
that success in drug courts has been credited by many drug court participants to their interactions
with the judge (Marlowe, Festinger, Lee, Dugosh, & Benasutti, 2006). Understanding what
makes these interactions effective, what the ‘dosage’ of judicial interactions should be, and

74
understanding what about the interactions is effective in the eyes of participants would greatly
benefit drug court practitioners. Further qualitative study may also allow for customization of
drug court interventions that allow for better outcomes.
Additional long term recidivism data would also make a compelling case for the further
institutionalization of drug courts. There are studies in the literature that point to the long term
effectiveness of drug courts in preventing recidivism (Finigan, Carey, & Cox, 2012), (Wilson,
Mitchell, & MacKenzie, 2006), (Krebs, Lindquist, Koetse, & Lattimore, 2007). While this sort
of longer term research over the course of many years may not be practicable for a dissertation
project, this kind of data collection combined with meta-analysis from multiple jurisdictions and
multiple courts nationwide would be a worthwhile project for government agencies and larger,
well-funded research groups. This recidivism data would not only assist with the acceptance of
drug courts as a policy intervention but also with the potential expansion of problem solving
courts into other spheres (as it already has with mental health courts, DWI courts and family
courts).
More experimental design research on drug courts would provide additional
understanding of how these courts work. Longitudinal, experimental design inquiries are present
in the literature, but they (most likely for the sake of practicality) follow one or two jurisdictions
(Deschenes, Turner, & Greenwood, 1995), (D. C. Gottfredson, Najaka, Kearley, & Rocha,
2006). The complications of experimental research with human subjects would certainly apply
here. The requirement to insure that all those who want the drug court intervention receive it
while isolating an adequate control group would present an ethical challenge. Also, defining the
demographic and other attributes (drug of choice, criminal record, previous treatment history,

75
etc.) would pose a challenge. However, this is just the sort of rigorous inquiry that would build
the credence and viability of drug courts over the long term.
Another area of inquiry that should be considered is an examination of drug court staff
attitudes and the implications of how their interactions affect drug court participants. An
instrument such as the Working Alliance Inventory (WAI) has been studied to measure the
strength of relationships between parolees and parole officers (Green et al., 2013) as well as in
traditional clinical settings. The WAI is a set of related measures that includes client, therapist,
and observer-rated versions (Mallinckrodt & Tekie, 2015). The instrument is administered to
client and service provider to give a quantitative measure of the impressions of each on the
therapeutic relationship. An instrument such as this administered in a drug court setting would
provide valuable, quantifiable insight into drug court therapeutic relationships that would
complement qualitative studies nicely.
As discussed in Chapter 2, application and development of further theoretical foundation
for drug courts is warranted. This more rigorous theoretical approach could address concerns
that drug courts are simply too different from each other for research in any one drug court to be
considered program evaluation rather than assessment of a uniformly applied intervention.
During the course of this project, another study was published linking Life Course Theory and
drug courts (Messer, Patten, & Candela, 2016). This author hopes to see additional theory
development in the form of exploratory and qualitative study in addition to the types of studies
cited immediately above in the near future. This sort of theory-based inquiry coupled with
empirical evidence will open up a new era of veracity and legitimacy for drug courts.

76
Conclusion
The proliferation of drug courts throughout the world over the last two decades presents
an opportunity and a challenge. The effectiveness of treating rather than punishing drug
offenders that has emerged in the literature is appealing on its face. However, more work needs
to be done to demonstrate their effectiveness and impact for the drug court movement to
maintain momentum and for the philosophy of treatment to spread to other areas of the justice
system. There is much that researchers still do not know and the questions of ‘how’ and ‘why’
drug courts work have not been sufficiently addressed. This research study is an examination of
secondary data from one drug court to attempt to correlate factors that contribute to success (as
defined by graduation) in drug court.
By utilizing a theoretical grounding in Life Course Theory, Social Capital Theory and
Recovery Capital Theory, the hope is to introduce an additional level of theoretical foundation
lacking in the current drug court literature. Results from the study demonstrate low to moderate
ability to predict drug court graduation using the factors studied. Among the factors found to
contribute to program success were participants having children, their employment status, 30-day
abstinence, age, and race. There is still a large amount of additional inquiry to be done to fully
understand the impact of drug courts on the well-being of the participants and on the success of
drug courts as a policy intervention.

