


1
Relationship Between Non-Affirmation of Gender Identity, Healthcare Stereotype
Threat, and Perceived Employment Inequities
Section 1: Foundation of the Study and Literature Review
Introduction
Transgender and gender diverse (TGD) employees make up 18% (Baboolall et al.,
2022) of the staff in healthcare organizations across the globe. There are perceived
employment inequities surrounding employee retention rates, lack of diversity in staff,
and discrimination including sexual harassment and hostile work environments in the
healthcare workplace culture for TGD employees. Non-affirmation or rejection of
someone’s gender identity is a microaggression seen in the workplace by transgender and
non-binary (TGNB) employees (Parr & Howe, 2020). According to Thoroughgood et al.
(2020), TGNB employees face many issues at their workplace, including discrimination
and harassment leading to devastating emotional consequences. Because some healthcare
organizations focus only on the sexual orientation of minorities, there are high turnover
rates and low productivity for TGNB employees (Liu et al., 2022). The Equal
Employment Opportunity Commission (2021) has seen an uptick in discrimination claims
for the broader lesbian, gay, transgender, queer, plus (LGBTQ+) community over the past
several years. In FY 2021, EEOC saw over 1,989 complaints by LGBTQ+ workers,
compared to only 808 complaints in FY 2013. Employee retention and job satisfaction are
low for TGNB employees (Thoroughgood, 2020), hurting the bottom line for healthcare
organizations and preventing them from striving for more diversity in their workforce.

2
Healthcare stereotype threat is pervasive for the TGD community and is
increasing as anti-transgender laws affect healthcare progress across the United States.
Transgender individuals face higher rates of healthcare stereotype threat due to high rates
of daily stress and the lack of resources in healthcare (Saunders et al., 2023). TGD people
are forced to advocate for their needs to obtain affirming healthcare due to the systemic
stigma of being trans-masculine and non-binary (Seelman & Poteat, 2020). All of this
leans toward the idea that healthcare is not a system built for TGD patients requiring their
resilience to obtain resources, culturally competent care, and healthcare needs met.
The specific research problem that was addressed through this study is the high
rates of discrimination TGD employees face in their healthcare organizations and
interactions with human resources. The other research problem is the healthcare
stereotype threat for TGD patients when seeking care throughout the healthcare system.
The challenge in healthcare organizations is that even though more diversity, equity, and
inclusive (DEI) policies and procedures exist across organizations, environments with
microaggressions lead to more barriers to obtaining a more diverse workforce and are
reflective of the TGD patients who receive care. This study will increase the knowledge
surrounding the relationship between gender affirmation, healthcare stereotype threat, and
perceived employment inequities equipping healthcare practitioners and human resource
professionals with resources to support TGD employees and patients.
Other components of Section 1 include the background, purpose of the study,
research questions and hypotheses, theoretical framework, nature of the study, literature
review, definitions, assumptions, scope and delimitations, significance, and a summary

3
and conclusion. The literature review provided in this section is a brief review and
synthesis of related articles and studies.
Background
TGD employees face high rates of discrimination in healthcare organizations due
to many factors. Non-affirmation of gender identity is one of the microaggressions (Parr
& Howe, 2020) that TGD employees face when going to work. Gender-based
victimization occurs when employees cannot affirm, or there is non-affirmation of their
gender identity with the ability to pass as cisgender leaving TGD employees to feel
marginalized or treated differently from their peers. Victimization is a more significant
systemic issue surrounding gender and sexual minorities receiving healthcare and
employed in healthcare.
LGBTQ+ employees and patients face high rates of harassment dominated by a
perceived culture that is heteronormative and cisgender. DiPalma (2021) stated that there
is a shift in cultural acceptance for LGBTQ+, but there is a need for more improvement
for those living as TGD. While many employees know someone who identifies as
lesbian, gay, bisexual, or even queer (Baboolall et al., 2022), many do not understand the
lived experience of or know a TGD person, which leads to microaggressions and a lack
of understanding (Liu et al., 2022). This gap in lack of understanding leads to low
satisfaction, decreased productivity, and high turnover for TGNB employees. TGD
patients are on the receiving end of an ethos of lack of understanding surrounding TGD
identities coming in for preventive care and treatment affecting their mental and physical

4
health and creating harm (Koch et al., 2020). TDG patients must endure stigma and lack
of resources to access medical care.
This study is needed to increase the understanding and awareness of the TGD
community for healthcare organizations that provide care and employment. By increasing
the knowledge surrounding the relationship between gender affirmation, healthcare
stereotype threat, and perceived employment inequities, healthcare administrators,
clinicians, and allied health professionals will have more tools and resources to interact
successfully with the TGD community. These resources will better equip them to be more
empathetic and compassionate while bringing awareness to their internal bias that has
caused harm and trauma in their prior interactions with TGD patients and employees.
Problem Statement
The problems to be addressed are employee retention, lack of diversity, and
discrimination in the healthcare workplace environment for TGNB employees and
patients. Additionally, the results of this healthcare environment encompass the lack of
affirming healthcare concerning their gender identity and healthcare stereotype threat.
Non-affirmation of gender identity is a microaggression seen in the workplace by TGNB
employees (Parr & Howe, 2020) and patients in healthcare. Negative healthcare outcomes
in combination with the stress of mental harm create a barrier for TGD patients to find an
affirming provider (Kattari et al, 2020).
According to Thoroughgood et al. (2020), TGNB employees face many issues at
their workplace, including discrimination and harassment leading to devastating
emotional consequences. Because some healthcare organizations focus only on the sexual

5
orientation of minorities, there are high turnover rates and productivity for TGNB
employees. During COVID-19, the loss of jobs meant a loss of health insurance for
sexual minorities and ultimately no access to healthcare due to the cost associated with
having access to care (Woolton, 2024). Healthcare stereotype threat increases when a
TGD person loses their job because they no longer can access a resource like health
insurance. They face the choice of food and shelter versus gender-affirming care and
medication.
The Equal Employment Opportunity Commission has seen an uptick in
discrimination claims for the broader LGBTQ+ community over the past several years.
Employee retention and job satisfaction are low for TGNB employees (Thoroughgood et
al., 2020), which hurts the bottom line for healthcare organizations and diminishes the
healthcare organization from striving for more diversity in its workforce. The lack of a
diverse workforce diminishes the ability to understand TGD patient needs and experience
when seeking care increasing the likelihood of increased healthcare stereotype threat.
Although researchers have investigated this issue, there is very little or no
literature on the roles of non-affirmation of gender identity, employment, and healthcare
stereotype threat to TGD individuals. This gap in the literature was the focus of this study.
Purpose of the Study
The purpose of this quantitative, retrospective, quasi-experimental study was to
examine the relationships between non-affirmation of gender identity, healthcare
stereotype threat, and perceived employment inequities in U.S. adults. The independent

6
variable was the non-affirmation of gender identity. The dependent variable was
healthcare stereotype threat and perceived employment inequities.
Research Questions and Hypotheses
The following research questions and hypotheses guided this study: RQ1:
What is the relationship between non-affirmation of gender identity and
healthcare stereotype threat?
H01: There is no statistically significant relationship between non-affirmation of
gender identity and healthcare stereotype threat.
H11: There is a statistically significant relationship between non-affirmation of
gender identity and healthcare stereotype threat.
RQ2: What is the relationship between non-affirmation of gender identity and
perceived employment inequities?
H02: There is no statistically significant relationship between non-affirmation of
gender identity and perceived employment inequities.
H12: There is a statistically significant relationship between non-affirmation of
gender identity and perceived employment inequities.
Theoretical Framework
The theoretical framework that guided this study is the sexual citizenship theory
created by T.H. Marshall (Rosich, 2020). The three elements of the model are (a) civil
society, (b) political society, and (c) the State or social society. Theories of structural
justice, like sexual citizen theory, are a subset of Marshall’s theory of social citizenship

7
(see Figure 1). Sexual citizenship theory focuses on the rights of civil society, such as a
person's right to work and seek healthcare for those who identify as TGD.
Figure 1
Sexual Citizenship Theory
The logical connections between the framework presented and the nature of the
study include theories of structural justice that examine concepts of heteronormativity,
homonormativity, and transmisogyny (Rosich, 2020) that affect workplace climate (civil
society) for TGD employees and patients obtaining healthcare. TGD employees face a
range of discriminatory biases in the workplace resulting in demotion or loss of
employment. With the loss of employment, the consequences are the inability to function
fully as an adult in the United States, which is the framework of sexual citizenship theory.
Additionally, TGD patients confront a healthcare system that has a lack of resources, high

8
levels of bias, and not enough culturally competent providers also in the sexual citizen
theory framework.
Nature of the Study
To address the research questions in this quantitative, retrospective,
quasiexperimental study, simple linear regression analysis was used to investigate the
correlation between non-affirmation of gender identity, healthcare stereotype threat, and
employment. The quantitative approach was ideal for this study, as it allows the gathering
of secondary data, which can be used to analyze the relationships between variables using
simple linear regression analysis. The retrospective approach signals the data were done
before this study. The study’s independent variable was non-affirmation of gender
identity. The dependent variables were healthcare stereotype threat and employment. The
data included were gathered from the Inter-university Consortium for Political and Social
Research (ICPSR) at the University of Michigan. Their secondary data were
predeidentified to ensure confidentiality. Variables related to non-affirmation of gender
identity, healthcare stereotype threat, and employment were exported as an Excel sheet.
After export, data analysis was conducted using simple linear regression to assess
relationships between the three variables.
Search Strategy
The following databases were accessed to obtain relevant literature: Taylor &
Francis, Thoreau, PubMed, EBSCOHost, and The International Journal of Transgender
Health. All sources were English-only text to reduce translation bias and peer-reviewed
studies that presented empirical data regarding key variables. This review did not include

9
doctoral dissertations and conference proceedings, as peer-reviewed literature was
accessible for discussion. Keywords were healthcare stereotype threat, gender identity,
minority stress, human resource management, DEI (diversity, equity, and inclusion)
policies, training, and transgender affirming. The literature review includes peerreviewed
resources published between 2013 and 2024. Key variables of the study frame the
literature review.
Literature Review Related to Key Variables and/or Concepts
Nonaffirmation of Gender Identity in Healthcare and Employment
TDG people face discrimination when they show up to work in healthcare
organizations when their gender is not affirmed, or it is rejected (Perales et al., 2021).
Discrimination is pervasive in healthcare for the LGBTQ+ community (Blackwell et al.,
2020), spilling to LGBTQ+ clients receiving care. Discrimination includes not being
addressed with the chosen name and pronouns, being harassed about how they express
their gender, being passed over for a promotion, having their workload diminished, and
being fired from their job. Safety of their employment becomes paramount when
compared to job satisfaction.
Safety for the employed TGD population includes the ability to affirm their
identity through gender expression (Hughto et al., 2020). Hughto et al. (2020) pulled data
from the 2015 US Transgender Stress and Health Study, in which 288 transgender
individuals over the age of 18 completed an online survey with 81% identifying as
transmasculine and 18.8% as transfeminine with non-binary identities included in both

10
categories with 96% of the participants disclosing their gender identity. The participants
were broken up into regions of the United States, with the West at 31%, the South at
26.7%, the Northeast at 26%, and the Midwest at 15.6%. Researchers found a statistically
significant relationship between gender affirmation experiences and several mental health
symptoms. The study assessed gender identity as cisgender, male and female, transgender,
female to male and male to female, and non-binary identities such as gender non-conforming
and non-binary. The question was asked about their medical affirmation and social
affirmation regarding their gender identity. The study focused on TDG individuals'
discrimination they experienced in seven areas including healthcare and whether they were
affirmed by their gender identity when they received care. Researchers scored their anxiety,
stress, and depression symptoms with mixed-effects models displaying self-reports of harm
and suicidality from before and after (p<.001) the start of the gender affirmation process.
Researchers found a link between mental health and gender-affirming procedures
concerning stress (p <.001), anxiety (p = .01), and depression (p =.01). Hughto et al. found
that the ability to affirm and express gender identity decreased depression and suicidality for
TGD people. The findings indicate the need for gender affirmation for the TGD population
to improve mental health.
Gender expression is the way a person displays their gender through the use of
clothing, mannerisms, and their voice through pitch and resonance (Sawyer &
Thoroughgood, 2017). Gender expression is perceived by coworkers (Davidson &
Halsall, 2016) as either male or female by other staff members due to the societal view of
only two genders. The binary perception of gender can create cognitive dissonance for
fellow employees and providers who may or may not have ever met a TGD person. A

11
lack of understanding or negative beliefs surrounding TGD people creates an
environment of uncertainty and, quite possibly, a safety concern for the employees and
patients.
With the current political landscape, many misconceptions around the TGD
community affect the healthcare industry, spilling over into patient care and employee
rights (Witt & Medina-Martinez, 2022). TGD people face high rates of unemployment,
housing crisis, and poverty due to misconceptions around their gender identity, requiring
nurses to empathically understand their needs for appropriate and competent care
(Wichinski, 2015). Healthcare professionals, then, must be educated on the additional
needs of the TGD population. Education then expands the cultural competence of the
environment to support all who work and receive care. However, the personal biases of
coworkers and providers can impede relationships, increase hostility in the workplace,
and create an environment where patients receive subpar care.
Bias around TGD employees’ gender identity creates threats to autonomy.
Consistent threats around gender identity and not feeling seen or heard result in hiding
gender identity in the workplace (Van Laar et al., 2019). The threat of being “outed” as
TGD requires the employee to deny their very existence and struggle with internalized
transphobia increasing the need for mental health support to overcome their personal bias
(Flynn & Bhambhani, 2021). The TGD employee is left feeling a lack of belonging to the
healthcare organization.
Lack of belonging in the workplace leaves TGD employees vulnerable to harm.
Healthcare continues to struggle with employees' psychological safety, meaning

12
discrimination runs rampant, where many are bullied, harassed, and belittled (Siad &
Rabi, 2021), opening space for TGD employees and patients to feel less than and not
affirmed. The lack of belonging creates a toxic and harmful environment for fellow
workers and the patients they serve. The harm cycle continues with stereotype threat,
creating an environment that lacks safety and belonging.
Belonging in the workplace means affirming the identities of fellow healthcare
colleagues in an organization. A healthcare environment that shows hospitality for
belonging and acceptance provides LGBTQ people a space to flourish and be present
(Newman et al., 2021). All humans inherit the need for belonging, as seen in Maslow’s
hierarchy of needs. TGD employees and patients feel valued and respected in a healthcare
environment that celebrates belonging.
Gender Identity in Healthcare and Employment
TGD employees and patients enter the healthcare environment with past
challenges relating to their gender identity. To fully understand the complexity of the
challenges, it is essential to define gender identity. Gender identity describes the
relationship between oneself and feelings about how one sees their identity, which can be
different from their outward expression of gender (Davidson, 2016). Gender identity is
tied to how a person feels about their role in society and is separate from their attraction
or sexual orientation to another person. TGD individuals know that entering healthcare
means they may only have binary choices on how they identify.
Healthcare is driven by a binary system that has been on a false notion that every
patient is female or male. This theory is harmful to the TGD community leading to hurt

13
and harm by the medical community and a feeling of being othered by identities such as
non-binary or genderqueer. In contrast, DNA is not female or male but karyotypes XX,
XY, XXY, and more (Vincent, 2019). Pragmatic views of gender are not straightforward
and can be used as microaggressions against the TGD community. However, when
language is introduced to healthcare professionals that includes a broader view of gender
and even sexuality, those they interact with feel a sense of respect and feel valued.
TGD people see gender identity as a spectrum, not a linear line where a human is
either female or male. Transgender is an overarching umbrella term split between binary
terms like transman or transwoman and nonbinary terms such as non-binary, gender fluid,
agender, and more (Green & Mauer, 2015). Transgender means a person does not identify
with the sex assigned at birth (Dahlen, 2020). These designations or identities require
healthcare providers and employers to examine how the employee and patient’s outward
appearance may differ and require less gendered notions.
Gendered notions or societal norms of gender focus solely on the belief that a
person is either female or male and is based on visualizing genitalia at birth. As
researchers have noted, gender and sex are different (Rouse & Hamilton, 2021), with sex
being tied to hormones, external sexual organs at birth, and genetic sex. On the other
hand, gender speaks to how someone is seen in their culture and society at large. These
differences can cause problems in healthcare because healthcare treatment and billing see
patients and employees who receive insurance as binary, either female or male (Wagner et
al., 2022). The binary constructs of the healthcare society do not match the current culture

14
of industrialized nations, pushing workplace policy changes to support TGD employees
and patients.
Western cultures tend to lean towards the binary gender theory (Thorne et al.,
2019). However, many indigenous cultures revere and celebrate more than two genders
creating conflicts in the healthcare system. Indigenous tribes across the Americas
recognize the term “two-spirit.” The term represents gender identity and sexual
orientation without assimilating to Western theory (Robinson, 2020) and Indian culture;
gender variance identities such as hijra, zenana, koti, kinner, and thirunangai (Ghosh,
2022) describe other genders in a cisgender colonized society. The cultural discrimination
with these identities spills over into the healthcare system when employees and patients
who identify with any number of TGD identities are not respected and even discriminated
against, adding to the challenges that TGD people face when staying employed and
receiving adequate care in the healthcare organization.
Challenges TGD People Face in Healthcare
TGD employees bring to work the burden of health disparities while taking care
of patients and working to stay present. They carry the burdens of homelessness,
discrimination, isolation, lack of healthcare access, substance abuse, and mental health
concerns into the workplace. TGD employees face high unemployment rates and tend to
work in low-paid positions (Leppel, 2021), resulting in community-based trauma
concerning their employment. Furthermore, workplace environments have become a
social determinant of health (Sherman et al., 2021). For TGD people, walking into their
daily job brings constant fear and dread surrounding their employment status and benefits

15
of health insurance, and ultimately staying safely housed. Furthermore, health insurance
does not ensure TGD safety in the healthcare environment.
A problem the TGD community faces is that health insurance is inherently binary,
forcing TGD people to fit into either the female or male identity leaving no space for non-
binary identities. Research has identified discrimination around insurance coverage of
gender-affirming care (Lerner et al., 2021) and non-binary individuals are less likely to
have affirmation of their gender in healthcare spaces (Reisner & Hughto, 2019), resulting
in employees and patients being unable to self-identify with their insurance and then
identified instead with their gender assigned at birth. The secondary data analysis of the
2015 Transgender Trans Survey (Lerner et al., 2021) pointed towards discrimination by
healthcare providers as the reason for barriers to healthcare utilization by the TGD
population in the United States, with 96% of the 21,930 TGD participants identified as
US-born citizens. The study found 22% of survey participants did not utilize healthcare at
all. Researchers looked at the relationship between avoiding healthcare and cost, invasive
provider questions (p<.001), refusal to provide affirming care (p<.001), verbal abuse
(p<.001), and provider’s lack of education to provide care (p<.001). The result is fewer
wellness visits and care by medical providers, adding more health crises’ and a lack of
mental health care. Health insurance for the TGD community must include coverage of
primary healthcare, including needs such as gender-affirming hormone therapy. Lerner et
al. (2021) pointed out the need for better education for providers to provide better care to
the TGD community. For many TGD individuals, living as their true selves and safely in

16
society means needing to pass as binary, leaving non-binary individuals less likely to fit
into the binary culture.
To pass means to be undetectable to others as anything other than cisgender
female or male (Doyle, 2022) or in a heterosexual relationship (Dixon & Dougherty,
2014). Passing helps some TGD employees navigate the workplace environment by not
bringing unwanted attention to their existence. By showing up as a binary gender, which
is socially accepted, TGD employees face less paranoia at work (Thoroughgood et al.,
2017). With these cultural norms, gender non-binary employees are then expected to
show up or express their gender as either masculine or feminine by cisgender colleagues.
TGD patients are seen as abnormal whether they pass or not due to the psychopathology
of their identity (To et al., 2020). The requirement to pass leaves TGD individuals with
more trauma and feeling less likely to belong to a team or even an organization providing
care.
Trauma for TGD people can include past trauma in healthcare, social situations,
workplace discrimination, and violence. Health and well-being are associated with a lack
of affirmation around gender identity (Doyle et al., 2021) and perceived discrimination in
the healthcare environment resulting in fear of safety, unemployment, and substance
abuse of TGD employees (Owens et al., 2022). Trauma, combined with repeated daily
work stressors, requires TGD people to be able to be present and reliable in their work
duties with or without additional resources to support their success. The emotional and
mental toll can result in unemployment and possible suicidal ideations for TGD
individuals.

17
Gender dysphoria is common for many TGD persons as a social determinant of
health, resulting in depression, anxiety, and self-harm (King & Gamarel, 2021).
Employees suffering from gender dysphoria or gender incongruence create minority
stress due to misconceptions and persecution of TGD individuals, where more support
and acceptance are needed (Piegza & Główczyński, 2022). While not all TGD people
suffer from gender dysphoria, challenges happen for those who do and are not supported
by their healthcare organization. As negative attitudes toward TGD people increase,
higher rates of anxiety and depression are soon to follow, adding to healthcare costs and
missed time from work.
Attitudes Around the TGD Population
Studies have shown a history of bias across health organizations and academic
medical institutions concerning the transgender community. With this, healthcare
professionals can help to advocate for their fellow TGNB colleagues and the patients they
serve. Liu et al. (2022) reported that doctors could use their clout along with their
upstream power and privilege to ensure policy change to support TGNB individuals
working and seeking care in their healthcare facility. Furthermore, privileges that include
the broader healthcare field have protection against HR policies that are not inclusive.
Enders et al. (2021) challenged leaders to address microaggressions when they happen,
not only during a performance evaluation. Policy advocacy and gentle nudges are some
ways that physicians and healthcare professionals can speak up against harm seen by
those TGD employees they work beside daily. Because doctors are held in such high

18
esteem, they can effect change on local and national levels within their professional
membership.
Many healthcare professionals fear saying anything (Canvin et al., 2023) because
of the lack of understanding of the TGD community, leaving TGD employees and
patients vulnerable to microaggressions. Canvin et al. (2023) analyzed qualitative data
from healthcare professionals who worked with the TGD community in London.
Providers felt they had inadequate training, fears of getting things wrong, lack of
experience or understanding, and the need for more training. The research showed that
conducting training in a non-judgmental space equipped healthcare professionals with the
tools and language to support the TGD community and overcome bias.
Healthcare professionals come with their belief systems and biases, which
translate into strained work relationships, including the inability to communicate and
work (Kanamori & Cornelius-White, 2016) with TGD employees. Having a hostile
working environment where microaggressions are present can create a feeling of not
belonging to the department or the organization, adding to the stress of TGD colleagues.
Along with biases, religious beliefs can also be pervasive throughout healthcare
organizations.
In 2016, it was estimated that about 14.5% of Catholic for-profit and non-profit
healthcare organizations in the United States (Khaikin & Uttley, 2016) shy away from
supporting or caring for TGD patients in their communities. Lawsuits by transgender
employees in religious healthcare organizations have popped up across the country
(Meyer, 2016), giving those employers religious freedom over Section 1557 of the

19
Affordable Care Act. The rulings allow faith-based organizations the freedom to take
away gender-affirming healthcare treatment coverage by insurance leaving TGD
employees and patients unable to have care covered and leaving them vulnerable to not
fitting in or feeling like they are welcome and supported.
Secular-based healthcare organizations can create hostile work environments for
TGD employees, as well. In the southeastern United States, transphobia and racism are
increased by conservative and evangelical environments resulting in high unemployment
rates, poor healthcare, and fewer social resources for TGD people (Johnson et al., 2020).
Religious-based healthcare organizations create more unsafe psychological space for
TGD due to past trauma and harm by established conservative religions (Scott et al.,
2021). Healthcare TGD employees end up in a position of constant harm or face
unemployment along with a lack of feeling of belonging because of their gender identity,
and patients feel unsafe to receive treatment.
Fitting in or feeling like the belong requires a binary gender expression for TGD
employees in healthcare. TGD employees will often attempt to change their gender
expression to fit in with their coworkers (Van Laar et al., 2019). TGD people do this by
presenting more binary or more masculine/feminine, like their cisgender cohort.
Appearing as female or male can harm the emotional and mental well-being of those who
identify as TGD. Furthermore, it perpetuates the stereotype of the binary system in the
healthcare environment adding more triggers to the employees just trying to do their job
and patients needing access to healthcare.

20
Transphobia in Healthcare and Employment
In the healthcare environment, transphobia is the best predictor of harm in the
TGD community. Transphobia, or the biases of transgender identities, can keep healthcare
professionals from being willing to learn and support TGD people (Stroumsa et al.,
2019). Those biases or transmisia keep TGD employees and patients from feeling
respected and accepted by the healthcare organization. Furthermore, it fosters a
healthcare environment where only cisgender employees and patients are supported.
Biases around the TGD community continue the progression of harm in healthcare.
Biases in healthcare create high rates of discrimination against minority healthcare
students. TGD medical students’ fear of affirming or disclosing their identity creates a
hostile environment in teaching hospitals (Giffort & Underman, 2016), furthering the
cycle of harm in healthcare. In an environment where all students are coming to learn,
TGD students hide their identity to fit into the cisgender culture. Healthcare misses out on
opportunities to learn from those whose lived experiences add to patient experience and
help to move past binary notions.
Healthcare is intrinsically binary-focused, founded on the notion that people are
either female or male. The binary notion is problematic for all identities because TGD
and intersex people find themselves in a situation where belonging to a team or
department becomes complicated. The binary theory is deeply entrenched in our society
(Thoroughgood et al., 2020) and the healthcare institution. Because healthcare treatment
is solely focused on female and male anatomy TGD people feel less than or abnormal
because of their physical anatomy. In turn, bias around bodies that do not fit in the box of

21
females or males leaves healthcare providers stuck between their fears and biases while
attempting to treat patients with dignity and respect.
Healthcare leaders in organizations often lack education on how to provide
appropriate care for the TGD community, resulting in ongoing microaggressions fueled
by unconscious biases. Unconscious bias is a stronger indicator than the education of
healthcare providers around the TGD community (Stroumsa et al., 2019), leading to more
harm to TGD employees and patients. Two hundred twenty-three clinicians, with 50.6%
being internists, 22.4% being family physicians, and 26.9% being ob-gyn practitioners in
the Midwestern United States, were surveyed with a 59% response rate. While most of
them treated at least one TGD patient (n=111, 49.7%), they did not have additional
education, and if they did it did not always address biases around TGD patients.
Researchers focused on health education (p=.292), transphobia (p<.001), and experience
with TGD patients (p=.259). Researchers found statistical significance that education did
not equate to knowledge, transphobia predicted knowledge. Microaggressions such as not
affirming identities, the use of chosen names and pronouns, and the assumption that every
employee is cisgender create an environment that is not supportive of employees and
patients who are TGD, and those microaggressions can be on top of widespread systemic
biases. Education can help address health disparities, however, bias around gender
identity does not always dissipate (Stroumsa et al., 2019). To prevent the harm caused by
these microaggressions, it is crucial to establish specific organizational policies that
prioritize inclusivity and address unconscious biases. This study enforced the need for

22
more education and self-reflection on conscious and unconscious biases when working
with the TGD population.
Numerous healthcare organizations have acknowledged their deficiency in
policies to tackle systemic biases and are now urgently striving to implement measures
that support their marginalized employees, including those who identify as TGD. The
lack of policies across healthcare organizations intensifies harm because TDG employees
report the lack of guidelines and enforcement of Title VII of the Civil Rights Act of 1964
that protects gender identity (Kleintop, 2019). Being TGD includes medical, social, or
legal transition, and the lack of policies leaves these employees without protecting their
identity (Westbrook & Schilt, 2014). The lack of policies leaves organizations without the
means to have a culturally competent systemic environment protecting anyone who is not
white, male, cisgender, or heterosexual.
Affirmation of Gender Identity
Cultural Competency in Healthcare and Employment
Cultural competency, although widely discussed in systemic environments like
healthcare, extends beyond a one-time effort or a mere notion. Cultural competency
requires consistent learning and updating views. For an organization to be inclusive, it
must have a diverse pool of employees and additional competency through creativity and
innovation (Hossain et al., 2020). Because higher levels of management in healthcare are
centered on cisgender white identities, the priority has been less than desirable, leaving
TGD employees stuck in less-than-affirming working environments. Cultural competency

23
necessitates going beyond simply educating staff about gender identity, racism, sexual
orientation, and issues faced by other underrepresented communities.
To effectively adapt to evolving language and new concepts, cultural competency
must be continuously updated and sustained. Due to the rapid pace and constant demands
of healthcare environments, health professionals face challenges in both delivering
patient care and ensuring equity among their staff and patients (Willging et al., 2019).
Unfortunately, education often neglects the inclusion of gender identity and sexual
orientation (Galupo & Resnik, 2016). The stress of working in healthcare can block
wellintentioned staff from alleviating their personal biases requiring cultural competency
to be more than an hour, once-a-year education. Allowing more staff practice and
reflection helps to understand the need for self-affirmation of identities for those
employed and seeking treatment at a healthcare organization.
Policy in Healthcare and Employment
Implementing gender-affirming policies for TGD employees is essential to foster
inclusive employee practices and ensure comprehensive insurance coverage for the
healthcare needs of all employees. While there has been a growth of DEI initiatives
across organizations, workplace buy-in is a requirement for success (McGregor et al.,
2019). Healthcare culture mirrors U.S. culture regarding bias around racism,
homophobia, and transphobia (Enders et al., 2021) and requires organizations to have a
strategic plan for more inclusion and affirmation.
Enders et al. (2021) researched Mayo Clinic’s DEI plan with a qualitative
approach to gather data around a DEI framework within the organization. One hundred

24
sixty-two participants encompassed their Health Services Research department. The staff
worked out of three of the Mayo Clinics located in Rochester, MN, Phoenix, AZ, and
Jacksonville, FL. The study participants shared ideas and feedback on the plan which
includes a two-step approach of increasing the belonging of underrepresented employees
and increasing staff diversity (Enders et al., 2021). Workplace environment focused on
training be the most important (p=.04) and review nudges (p=.01). The plan had two
goals, increase an overall sense of belonging and overall diversity throughout the Mayo
Clinic (p≤ .05). While this approach may seem too simplistic, it is a start to deeper
conversation and curiosity on how to get more input from staff and leaders in a healthcare
organization. Reviewing policies and procedures is only sometimes the first step in
building a more affirming and inclusive organization.
While Title VII of the Civil Rights Act of 1964 serves as a foundational starting
point for reviewing employee policies, it falls short of adequately protecting TGD
employees within healthcare organizations. Title VII broadly covers discrimination based
on gender identity but does not include policies or steps the administration must take to
protect TGD employees (Elias, 2017). Leaders and HR managers are then left to devise
policies to protect TGD employees and all other employees from discrimination. If the
organization needs TGD employees in leadership or diversity in the workplace, TGD
people are included in the conversation where input is essential. Moreover, cisgender
leaders lose the ability to have the lived experience needed to comprehend TGD
employee experiences fully. Having a solid workplace culture around all identities can
help support those underrepresented.

25
While Title VII offers certain protections for TGD employees, the Americans with
Disabilities Act (ADA) provides a more comprehensive level of security. The ADA offers
shelter in public accommodations and entities like bathroom protection, gender
expression, and time off for medical needs surrounding gender dysphoria and
genderaffirming care (Szemanski, 2020). ADA compliance in healthcare facilities is a
federal act supplying broader protections for TGD employees. Having the ability to
support TGD employees with federal policies helps in the creation of a workplace policy
that affirms all identities.
Healthcare policy for TGD patients helps to ensure they receive the best holistic
care. The ability to receive affirming holistic care requires the need for policies that
protect TGD patients including policies that address discrimination, health insurance
coverage, gender-affirming hormones and treatment, mental health care, and access to
changing legal documents (Goldenberg et al., 2020, Perone, 2020). Additionally, the need
for a review of structural policies, staff education, and continued access to care needs to
be considered in holistic care (Goszkowicz & Davis, 2023). These require hospital
administration to draft and execute a safety plan for TGD patients entering their
healthcare facility. Starting with federal discrimination policies in the Affordable Care
Act (ACA), such as Section 1557, gives healthcare organizations a starting foundation for
enacting policies that support the TGD community. Section 1557 of the ACA prohibits
discrimination in healthcare based on sex including gender identity supporting the TGD
communities’ need for protection while the ADA offers protection for receiving
genderaffirming care in healthcare organizations.

26
Religious exemptions cause harm to the TGD community when seeking
healthcare at faith-based health organizations. The Religious Freedom Restoration Act
(RFRA) prioritizes religious preferences over discrimination around federal laws such as
Title VII or Section 1557 of the ACA (Blazucki, 2023). RFRA opens the door for
religious healthcare organizations to deny healthcare and deny employees jobs or
promotions to TGD people. Ultimately resulting in harm and additional health disparities
for those who identify as TGD.
Self-Affirmation
The capacity to validate one’s own identity, such as gender, serves as a valuable
asset for an employee and patient entering a healthcare organization. Being able to show
up as one’s true authentic self is the key to self-affirmation (King & Gamarel, 2021;
Doyle, 2022, Rood et al., 2017). The capacity to express one’s gender identity is a unique
journey to a consistent determinant of health. The ability to express that gender can factor
in bias, racism, and discrimination resulting in trauma for TGD people (Sevelius, 2013;
Reisner et al., 2016). Employees, patients of color, and those TGD who present nonbinary
can find themselves at the end of microaggressions and biases by those who do not
understand or accept identities outside of the binary genders. The potency of
selfaffirmation diminishes when the ability to express it is restricted or denied for TGD
individuals.
By endorsing the ability to self-identify, people demonstrate support and
celebration of the diverse identities present in healthcare. Transitioning is a process of
living as one’s true self (a) legally: changing a person’s legal name; (b) medically:

27
surgical, or through gender-affirming hormone therapy and care; and (c) socially: by
expression of clothing, voice, and mannerisms (Thoroughgood et al., 2020). Supportive
healthcare cultures accept and celebrate TGD transitions through policy and approval of
procedures by the employee’s health insurance (Huffman et al., 2021). Ensuring people
have a voice and a seat at the table guarantees that they are both heard and valued.
ERGs
Despite the organization's overall need for greater representation, Employee
Resource Groups (ERGs) should strive for increased diversity, specifically by including
more individuals from the TGD community. ERGs, which include TGD voices, have
been used in organizations to improve DEI procedures and culture to improve the
inclusivity of their staff (McNulty et al., 2018). Furthermore, one of the metrics in the
Human Rights Campaign Healthcare Index (2022) scores the organization on whether or
not the company has an LGBTQ+ ERG and a community council. The community
council and ERGs influence the healthcare organization for both employee culture and
patient care for those they serve. At the same time, allies advocate and support their peers.
Healthcare Stereotype Threat
The theories of minority stress and stereotype threat center around the detrimental
impact of bias in healthcare. Minority stress is pervasive in healthcare leading to health
disparities (Burgess et al., 2010) and is the framework that appears with incongruency
between sexual minorities and dominant culture. Healthcare stereotype threat judging a
patient based on perceived unhealthy lifestyles and inferior intelligence (Abdou et al.,
2016). Healthcare stereotype threat others those who identify as a sexual minority like the

28
LGBTQ+ community, creating a space of judgment and bias for TGD individuals. The
presence of healthcare stereotype threat has a profound impact on both patients and
employees within the healthcare environment.
The persistence of healthcare stereotype threat in the workplace goes unnoticed
and concealed by hospitals and healthcare administration, permeating throughout
organizations. Research shows that healthcare professionals have overt and covert biases
toward the TDG community (Nadal et al., 2016). The biases the authors identified
included explicit and implicit, which are not always apparent to the person committing
the microaggression. The unconscious behavior causes harm to the TGD person, and the
aggressor’s behavior may not be held accountable due to the fear and isolation TGD
people feel because of the injury. The race and income of the TGD community can further
intensify the healthcare stereotype threat.
Given the intersectionality of TGD individuals’ identities, race assumes a
prominent role in shaping the healthcare stereotype threat. Researchers have identified a
correlation between race, gender, and sexual orientation in communities of color (Thorpe
et al., 2022). Thorpe examined secondary data specific to sexual identity and minority
stress in healthcare. One hundred forty-two Black and biracial cisgender females living in
the United States were asked about gender conformity and sexual identity concerning
exposing their identities to healthcare providers. Out of the participants, 45.6% identified
as bisexual, and 40.8% identified as lesbian/gay. While this study did not specifically
focus on gender identity, researchers found a significant correlation between Black
cisgender women who presented more neutral or masculine and healthcare stereotype

29
threat (p=.04). Results showed those whose gender identity is gender non-conforming
have higher levels of stigma in accessing healthcare (p=.03). A missing data point in this
study was the absence of Black TGD voices. Being TGD and BIPOC poses an even more
significant threat of bias and discrimination due to historical stereotyping and
victimization in a healthcare environment. Numerous DEI initiatives within healthcare
organizations are presently addressing racism and income disparities through the lens of
healthcare stereotype threat.
In healthcare settings, unconscious bias often occurs, leading to detrimental
effects on both employees and ultimately impacting patients. Microaggressions and the
suppression of gender identity and sexual orientation increase triggers of TGD across an
organization (Thorpe et al., 2022). Employees are then forced to deal or cope with the
stereotypes and stigma of being TGD every time they enter their workplace and TGD
patients fear accessing care. This burden affects the person as well as the organization
with absenteeism, mental and medical crises, and eventually loss of job or demotion in
work. Healthcare organizations incur hidden costs related to the recruitment of additional
staff, educational efforts, reputation deficits in terms of diversity, and the presence of a
hostile work environment.
Race
Healthcare stereotype threat is a comprehensive theory that examines biases and
stereotypes, yet it becomes problematic with the intersections of identities of race and
gender. Diving deeper into microaggression theory, a reader notices that personal
interactions filled with one-off comments or microaggressions converge (Arayasirikul &

30
Wilson, 2019) on the TGD community during their time at work or access to healthcare,
creating a dangerous environment for their health and well-being. According to the
research of Arayasirikul and Wilson (2019), 38 transwomen 16-24 years of age in
Chicago and Los Angeles shared their introductory work experiences and how their
identities were perceived in the workplace. The mean age of participants is 20.95 with
34.2% identifying as Black, 13.2% identifying as White, 15.8% identifying as Asian
American/Pacific Islander/Native American, and 23.7% identifying as Latino. The
qualitative study found a significant intersection of transmisogyny as a structure of
oppression by forcing TGD to pass which requires a medical transition. Workers who
could pass as cisgender had better workplace experiences versus those who were early in
their transition and faced transmisogyny and microaggressions for staff and clients.
The term transmisogyny, coined by Julia Serano in the mid-2000s, defines the
intersectionality of the biases of “transphobia, misogyny, and racism” (Whipple, 2021)
and has become a way to highlight the stereotypes and struggles of black TGD identities.
Researchers (Arayasirikul & Wilson, 2019) identified the passing of the complex (Figure
2), which is a continuous loop of transition work of passing, and the discrimination that
comes from not passing. TGD people not only have to overcome stressors around
transphobia but systemic racism is seen across the healthcare organization, once again
requiring TGD individuals to bear the burden of being resilient. TGD resilience comes
with high levels of mental health challenges, with substance abuse leading to
unemployment within the TGD community.

31
Figure 2
The Passing Complex (Arayasirikul & Wilson, 2019)
Trans women of color are less likely to be hired, creating housing and mental
health encounters leading to unemployment and housing instability. In the social
hierarchy of TGD identities, BIPOC women and feminine transgender individuals face
more violence and homicide due to systemic racism and transphobia, leading to fewer
employment opportunities, abuse, and housing insecurities (Wesp et al., 2019). The cycle
of black and brown sexual objectification creates more harm and less ability for
employment or access to healthcare. The TGD person’s healthcare then suffers from the
lack of lived experiences of BIPOC TGD employees and the inability to support patients
in that demographic. The lack of employment opportunities, housing, and access creates
income insecurities for BIPOC TGD individuals.
Self-affirmation of race supports black and brown TGD employees and patients.
Positive encounters in healthcare settings, such as self-affirming race and gender, lower
stereotype threats for BIPOC individuals (Taber et al., 2016). Furthermore, TGD
employees in rural areas and southern communities are less likely to support Black

32
employees (Smart et al., 2020). Healthcare organizations, where race is celebrated versus
environments where racism is present have better job satisfaction and fewer mental health
crises. In cases where stereotype threat becomes deeply ingrained in healthcare culture, it
inevitably results in unemployment which leads to income loss.
Perceived Employment Inequities
TGD live in fear that they will lose their job due to their gender identity or
expression of their gender. Discrimination is a concern for gender minorities because of
their gender identity creating an unsafe environment to self-identify on resumes and job
applications (Cabacungan et al., 2019). Moreover, disabled, gender minority employees
fear isolation and stress due to exposing their gender identity at work (Dispenza et al.,
2019). The perception of how their gender identity will be embraced or rejected adds
another layer of concern surrounding their employment opportunities or status at their
current organization creating perceived employment inequities. How the TGD employee
is perceived by their co-workers is a daily stress carried throughout their employment
journey.
Healthcare environments may be culturally competent and still have room for
improvement with TGD employees. TGD employees reported perceptions around their
visibility and ability to be out as themselves brought concern and worry about their equity
in the healthcare workplace which aligned with concerns by their cisgender co-workers
about TGD employees (Katz-Wise et al., 2022). Updated policies and continuing
education must continue to address improvements around employment inequities. Growth

33
areas in healthcare are felt by all employees in the arena of diversity, equity, inclusion,
and justice.
The rise in hostile work environments, the enactment of anti-transgender
legislation, and past instances of discrimination all contribute to the challenges faced by
TGD people in coping with the stigma associated with their identity. Resilience among
those in the TGD community is consistently noted in research (Van Laar et al., 2017).
However, it does not remove the constant discrimination the TGD employee faces when
entering a work environment and patients needing and receiving care. TGD individuals
face daily misunderstandings about their gender identity and expression of gender. They
must justify names, pronouns, and how they dress, walk and talk. TGD folks of color are
forced to combat elevated levels of discrimination because of stereotypes and biases
rooted in racism within healthcare organizations.
Income
In addition to facing unemployment, TGD people encounter additional challenges
such as lower wages and mental health crises. Workers who identify as TDG have lower
wages than their cisgender and lesbian, gay, and bisexual counterparts, leading to poor
mental health (Owens et al., 2022). Minority stress puts TGD employees in a position of
feeling unstable in their low-paying job, further exacerbating the worker’s mental health.
Additionally, TGD individuals have seen higher rates of discrimination in the healthcare
environment (Reisner et al., 2015). Healthcare stereotype threat overshadows the TGD
population's employment experience while attempting to do their low-paying job. The
bias and employment inequity overshadowing creates stress that negatively impacts the

34
mental health of workers, perpetuating a cycle that increases the risk of job loss,
substance abuse, and various social determinants of health.
Having a high level of education does not necessarily translate into increased
employment opportunities, in so doing impacting the income of TGD employees. TGD
people in states where there are transgender rights have a better chance at having a job,
and TGD employees tend to have more education than their cisgender counterparts, but
laws drive employers when hiring and wages (Leppel, 2016). Researchers note that laws
propel employment and wages higher or lower for the TGD community regardless of
degrees and education, even though they have more. Additionally, income is wielded both
as a tool for and against TGD employees, further aggravating income instability across
the board.
Summary of Literature Review
TGD people face discrimination in healthcare which often spills over into their
employment in healthcare organizations (Perales et al., 2021; Witt & Medina-Martinez;
2022). Gender identity plays a large role due to the ability to affirm gender identity
(Davidson, 2016; Doyle et al., 2021; Hughto et al., 2020; Sawyer & Thoroughgood,
2017) through expression, names, & pronouns at work. Bias in healthcare also plays a
role in the discrimination of TGD people (Flynn & Bhambhani, 2021; Stroumsa et al.,
2019; Van Laar et al., 2019). All this leaves TGD employees with feelings about their
safety (Siad & Rabi, 2021) and belonging (Newman et al., 2021). For TGD employees,
the healthcare workplace can wind up being an unhealthy environment to thrive (Doyle et
al., 2021; King & Gamarel, 2021, Lerner et al., 2021; Sherman et al., 2021) due to the

35
cultural norm of being cisgender (Doyle, 2022; Thoroughgood et al., 2017, 2020; Van
Laar et al., 2019). Healthcare leaders and professionals can improve the healthcare
environment through education (Enders et al., 2021; McGregor et al., 2019), addressing
microaggressions (Arayasirikul & Wilson, 2019; Canvin et al., 2023; Stroumsa et al.,
2019, Thorpe et al., 2022), and policy changes (Elias, 2017; Kleintop, 2019; Liu et al.,
2022; Szemanski, 2020). Overall, discrimination and bias around gender identity require
further consideration and research as a means of addressing and improving the needs of
the TGD community in healthcare.
Definitions
Non-affirmation of gender identity is the inability to affirm someone’s gender
identity using a chosen name, pronouns, and recognition of gender (Reisner et al., 2020).
Healthcare stereotype threat is a framework that describes negative stereotypes
around healthcare evaluation, treatment, and diagnosis by clinicians based on one’s social
group (Saunders et al., 2023).
Perceived employment inequities is a term that refers to the feelings employees
have based on their employment status based on the biases of their social group resulting
in demotion and termination or inability to be hired (Thoroughgood et al., 2017).
Cisgender is a term that refers to people whose gender identity aligns with their
sex assigned at birth (Goldbach et al., 2021).
Gender diverse is a term for a person whose gender identity or gender expression
does not conform to society’s definition of binary male or female gender norms (Rusow
et al., 2022).

36
Heteronormative is a system and a viewpoint that heterosexuality and binary sex
are the only sexuality and gender identity held as the cultural norm for all family
dynamics (Goldbach et al., 2021).
Homonormativity is adding the privilege, like same-sex marriage, of heterosexual
ideas and norms onto the LGBTQI+ community (Stewart, 2020).
Transgender is a term that refers to people with a gender identity that does not
align with their sex assigned at birth (Goldbach et al., 2021) and serves as an umbrella
term for the broader community (Green & Maurer, 2015).
Transmisogyny targets the transgender community of color with the intersectional
view of transphobia and misogyny (Boe et al., 2020), focusing on sexualizing and
fetishizing those whose gender identity is female or feminine expressing (Serano, 2021).
Assumptions
The assumptions in the study were that TGD employees in healthcare described
the workplace environment as their experience, the ability to affirm their gender identity,
and significant components surrounding workplace culture without the fear of retribution.
Additional assumptions include correct data collection and input by researchers without
bias and employees sharing their experience without the fear of workplace retaliation.
The experiences were necessary to measure the relationship between healthcare
stereotype threat and non-affirmation of the TGD lived experience within healthcare
organizations.

37
Scope and Delimitations
The scope of the study was limited to generalizations across healthcare
organizations. Each healthcare organization may have different experiences and
workplace cultures. Healthcare stereotype threat validity may vary based on the response
rate of staff and the TGD community regarding the feeling of safety to disclose their
gender identity, received bias, and harm. Perceived employment inequities can be felt at
any organization, for any TGD employee, based on their specific workplace environment.
Furthermore, the data set focused on the TGD community and does not represent all TGD
people and their lived experiences.
Limitations
Limitations include references from multiple healthcare environments such as
hospitals, clinics, pharmacies, and healthcare billing offices but the data did not provide
specific job titles or categories within healthcare organizations. Other limitations include
all TGD identities not specified in the dataset that excludes non-binary identities
terminology outside of non-binary and genderqueer, which excludes many more gender
identities. The measures used to address the limitations were the generalizations for
broader healthcare organizations which included using job titles such as clinicians,
healthcare professionals, and administrators for commonality. Employment inequity is
also generalized based on responses that were the perceptions of TGD individuals
working in the United States not always specific to healthcare. Other measures include
using TGD to encompass binary and non-binary transgender individuals.

38
Significance
The results of this study could potentially contribute to an examination and
explanation surrounding the healthcare stereotype threat for the TGD community in the
healthcare organization when they disclose their gender identity. Previous studies such as
the U.S. transgender survey in 2015 and 2022 focus on whether the TGD employee was
fired or demoted from their job (Leppel, 2021) and focus on bias and discrimination the
community lived through on a broader scale without affirming their gender identity. The
study identified the significant relationship between healthcare stereotype threat in
healthcare environments with TGD employees and patients. As such, the study may
potentially provide better clarification of the harm TGD individuals face in healthcare and
other industries around the affirmation of their gender identity along with the ability to
live their true authentic lives. This potential implication of this study will increase
understanding and awareness for those in healthcare to be a beacon of support to the
TGD community they serve and employ.
Summary and Conclusions
TGD people are continuously discriminated against in the healthcare environment
(Casey et al., 2019). They cannot affirm their gender identity due to bias and stereotypes
in and out of work (Reisner et al., 2016; Van Laar et al., 2019). The purpose of this
quantitative retrospective quasi-experimental study was to examine the relationship
between non-affirmation of gender identity, healthcare stereotype threat, and perceived
employment inequities of TGD people in healthcare organizations. This study will fill in
the gaps in the current literature to extend knowledge of awareness and provide more

39
support to the TGD community in healthcare organizations. This section identified the
supportive literature review, the purpose of the study, and the research questions. The
following section will include the design and methodology that guide this study.

40
Section 2: Research Design and Data Collection
Introduction
The purpose of this quantitative retrospective quasi-experimental study was to
examine whether there is a relationship between the non-affirmation of gender identity,
healthcare stereotype threat, and perceived employment inequities concerning employees
in healthcare systems and organizations. The variables are non-affirmation of gender
identity, healthcare stereotype threat, and perceived employment inequities.
Nonaffirmation focuses on the gender identity of the employee and patient. Healthcare
stereotype threat sheds light on the gender and sexual orientation of the employee and
patient. Perceived employment inequities center around their status only as an employee.
While TDG people face higher rates of discrimination, this study focused on the
culture of healthcare organizations where TGD patients and employees face inequities,
verbal abuse, and sexual assault. Conducting this study shed light on employee policy and
the treatment environment in healthcare organizations that affect the status of TGD
employment and the care TGD patients receive. All variables were gathered from
secondary data collection from the TransPop survey. Collected data involved using
correlation analysis via Statistical Package for the Social Sciences (SPSS) for Windows
Version 29, and descriptive statistics were calculated.
This section includes the research design and rationale for choosing a quantitative
method of research, the methodology will be explained, threats to validity will be
assessed with the final summary of the findings, and the end of this section will discuss

41
research design and collection.
Research Design and Rationale
This retrospective, quasi-experimental, quantitative study was designed to
examine the relationship between the independent variable of non-affirmation of gender
identity, and the dependent variables of healthcare stereotype threat and perceived
employment inequities. Because the variables in this study are identified and measurable,
the quantitative method is applied to the purpose of the study. This retrospective,
quasiexperimental was used to establish cause and effect because the data has already
been used in previous studies where there has already been intervention (White &
Sabarwal, 2014). For the field of study, the retrospective, quasi-experimental quantitative
research design was chosen to establish possible relationships between TransPop study
variables. The correlational study is the most logical for these specific variables from the
dataset, for this study.
This retrospective, quasi-experimental, quantitative study used a secondary
dataset collection from a survey from 2016-2018 specific to the TGD community and
their perception of their employment and healthcare access. The quasi-experimental
design was used in this study, with no time or resource constraints.
The purpose of this study was to examine any relationships with the
nonaffirmation of gender identity, healthcare stereotype threat, and perceived
employment inequities which are numerically measured for the secondary data source.
Data were received from people living in the United States.

42
Methodology
Population
In the TransPop survey from 2016-2018, the combination of transgender and
cisgender created one dataset. The transgender sample was N=274 and the cisgender
sample was N=1,162 with a combined total of N=1,436 across the United States. The
secondary data were collected from the TransPop survey. In the United States, it’s
estimated that the TGD population of adults 18 years and older is about 1.3 million
people, .5% of the population (Herman et al., 2022). The term transgender is a person
who does not identify with the sex they were assigned at birth (Dahlen, 2020). Because
the non-binary and genderqueer population data has not always been captured in US
census data until recently, this number is an estimate. Using the CDC’s Behavior Risk
Factor Surveillance System (BRFSS) survey, they report 38.5% (515,200) identify as
transgender women, 35.9% (480,000) identify as transgender men, and 25.6% (341,800)
identify as nonbinary/gender nonconforming (Herman et al., 2022) across the United
States.
Sampling and Sampling Procedures for Data Collection
The focus of the study was on a random sample of TGD employees throughout
the United States in 2016-2018 This study examined the variables using statistical tests
based on the secondary source of the TransPop Survey focusing specifically on
nonaffirmation of gender identity, healthcare stereotype threat, and employment.
Correlational methods of research are intended to determine the intensity of the
connection between variables (Frankfort-Nachmias et al., 2021). The sampling strategy

43
that was deployed was probability sampling which was random with known non-zero
probability. This study aims to add gaps in the literature and expand knowledge about
TGD employees in healthcare.
The original study goal was to get a representation of the TGD population in the
United States focusing on health outcomes, behaviors, institutional discrimination, and
other health-relevant domains based on personal perception. The TransPop was the first
national probability sample in the United States. The study is a combined dataset of two
data sources with one being TGD-only respondents, and the other being cisgender
respondents. The sample weight applied to the cisgender population is 50x the TGD
population. Bias surrounding data collection was twofold: a) target characteristic-TGD
and b) target community-LGBT. Recruitment and screening were performed by Gallup
Inc. using two methods:
1. US Adults using random digit dialing on cell and landline phones were
contacted and asked if they identified as lesbian, gay, bisexual, or transgender.
2. Shifted to address-based sampling by mail or online survey where Gallup sent
out surveys based on address.
Sampling inclusion included 18 years of age, the minimum of sixth-grade
education, and English speaking. The exclusion was Spanish speaking (5% of
participants), fifth-grade education and lower, and youth 17 years old and younger based
on the inability to consent legally. Each caller was then asked if they identified as LGBT,
if yes response, they were asked their sex assigned at birth and gender identity.

44
Respondents who identified as transgender served as the transgender sample. Those who
did not identify as transgender served as the cisgender sample. Participants were placed
in regions where they lived. Those regions include New England, Middle Atlantic, East
and West North Central, South Atlantic, East, and West South Central, Mountain, and
Pacific. Consent was assumed by filling out the survey or responding to questions asked
to each participant. Due to the privacy of disclosure, participants were not asked to sign a
consent form. In the second phase, respondents received a $25 gift card if they completed
the survey online or $25 cash if they mailed the survey back to Gallup.
The TransPop dataset is publicly available on the ICPSR at the University of
Michigan website. The study protocol was reviewed and approved by Gallup IRB and
UCLA IRB. The study collaborated with Columbia University, the University of Texas at
Austin, the University of California at Santa Cruz and San Francisco, the University of
Arizona, Surrey University, UK, and the University College of London, UK. These
collaborations included academic and professional input and feedback from TGD leaders,
researchers, and healthcare professionals.
A G* Power analysis was performed by using G*Power software version 3.1.9.7.
Input included a medium effect size of 0.15, an alpha error of probability of 0.05, a power
of 0.80, and one predictor. Based on the calculations, the necessary sample size for each
separate variable with statistical significance was 55. The available number of
participants is 252, which is adequate to achieve statistical significance and detect a false
null. With these tests, the minimum sample will support or disprove the statistical

45
significance of the research questions. Statistical significance can also rule out the null
hypothesis in this study.
Instrumentation and Operationalization of Constructs
The main data set used in the study is the TransPop survey from 2016-2018,
published in 2021 by Ilan Meyer. The goal of the study was to provide researchers with a
sample of the transgender population including basic demographics and examine health
outcomes and institutional discrimination (Meyer, 2021). Data for this study were
obtained publicly through the ICPSR at the University of Michigan website where no
permission was needed. The data was extracted from the website into an Excel
document. Specific data focused on non-affirmation of gender identity, healthcare
stereotype threat, and perceived employment inequities by use of sexual identity, race,
and gender minority. This dataset expanded upon another dataset, the US Trans Survey of
2014, and validated scales of the TransPop survey that measured the identity, stress, and
health of the transgender population in the United States.
Non-affirmation of gender identity is the independent variable. The dependent
variable is healthcare stereotype threat and perceived employment inequities. Survey
participants were instructed to choose their level of agreement with statements of the
quantitative variables from a 5-point Likert scale, ranging from “strongly disagree” to
“strongly agree.” The variables were recoded using a discrete count from zero to the total
sum score amount for each variable.

46
Nonaffirmation of Gender Identity
The variable for non-affirmation of gender identity looks specifically at the
question surrounding the perception of gender and gender expression. Gender conformity
for TGD people includes perception of gender expression or physical appearance and
non-affirmation of gender identity by others. Participants were given four statements
using a 5-point Likert scale in which they had to state whether they “strongly disagreed,
disagreed, neither agree nor disagree, agreed, or strongly agreed” to the statements. The
original data set used 1 for “strongly disagree,” 2 for “disagree,” 3 for “neither agree nor
disagree,” 4 for “agree,” and 5 for “strongly agree.” Using a recoded sum score for each
survey participant between 0-24. Zero denotes the participant has the least affirmation
and 24 denotes the participant has a strong affirmation of their gender identity. Strong
affirmation means that the TGD person felt affirmed in their gender identity, gender
expression, pronouns were respected, could “pass” regarding the gender identity, and
whether they felt understood as a person.
Healthcare Stereotype Threat
When the participants sought out healthcare, judgment, bias, and negative
diagnosis during their visits were asked by the researchers. Healthcare stereotype threat
refers to discrimination against TGD participants based on their sexual identity, and
gender minorities including BIPOC. The sexual identities include sexual minorities other
than heterosexual, lesbian, gay, bisexual, queer, same gender loving, asexual, and
pansexual. Gender identities include trans men, trans women, and trans-GNB (gender
non-binary). Participants were given four statements using a 5-point Likert scale in which

47
they had to state whether they “strongly disagreed, disagreed, neither agree nor disagree,
agreed, or strongly agreed” to the statements. The original data set used 1 for “strongly
disagree,” 2 for “disagree,” 3 for “neither agree nor disagree,” 4 for “agree,” and 5 for
“strongly agree.” This variable of healthcare stereotypes will include healthcare
experiences using a recoded sum score for each survey participant between 0-16. Zero
denotes the participant with the least healthcare stereotype threat and 16 means strong
healthcare stereotype threat. Strong healthcare stereotype means the TGD patient felt
judged negatively, worried about negative health interactions, receives a negative
diagnosis when seeing a provider, and is a negative stereotype for the TGD community.
Perceived Employment Inequities
The perceived employment inequities variable spotlights the employment status
of the TGD employee on how often the employee was fired from their job, denied a job,
denied a promotion, or received a negative evaluation based on their perception.
Furthermore, the variable looks at the outcome of employment focusing on being fired,
denied a job or promotion, or receiving a negative evaluation for each survey participant.
The scale used for these statements is how often the employee was fired, denied a job or
promotion, or received a negative evaluation with 1 being “never,” 2 being “once,” 3
being “twice,” and 4 being “three or more times.” A recoded sum score between 0-6. Zero
denotes the participant had no employment issues and 6 means three or more issues such
as termination, being denied a job or promotion, or receiving negative evaluations. The
two variables being used to measure negative employment outcomes record the number
of times fired, demoted, etc. as 0, 1, 2, or 3 or more. Even though there is no true count

48
for people fired more than three times, these represent a relatively small portion of the
sample (around 10%). The survey questions were treated as quantitative variables by
simply adding the two questions of how often the employee was denied a job or
promotion, negative feedback, or fired to get a rough measure of negative employment
outcomes. This biased the results towards being more conservative since those with more
than three firings or demotions were coded as having no more than three.
Data Analysis Plan
The data were exported from Microsoft Excel with the statistical analysis done
using SPSS (version 29). Data exploration started by preprocessing the variables and
removing all missing data and outliers to have a clear and concise data set and to ensure
the validity of the findings. The examination of the data was restricted to specific
questions about being fired, terminated, and denied a promotion. Using SPSS, the data set
was cleared of any missing data to ensure reliability. Demographics of the sample include
adults 18 years and older who identify as transgender or gender non-binary.
The data analysis was completed using a simple linear regression analysis, to
answer both research questions. Simple linear regression was appropriate for this study
because it establishes if there is a relationship between one independent and one
dependent variable. In this case, the independent variable is non-affirmation of gender
identity, and the dependent variables are healthcare stereotype threat and perceived
employment inequities. These three variables were created for the analyses as follows.
Tables 2, 4, and 6 in Chapter 3 refer to the TransPop survey questions that contain
data for the variable of non-affirmation of gender identity, healthcare stereotype threat,

49
and perceived employment inequities. Participants were given these statements using a
5point Likert scale in which they had to state whether they “strongly disagreed,
disagreed, neither agree nor disagree, agreed, or strongly agreed” to the statements. The
original dataset used 1 for “strongly disagree”, 2 for “disagree”, 3 for “neither agree nor
disagree”. 4 for “agree” and 5 for “strongly agree”. Scores were recoded to range from 0
to 4, then added together for a single index, resulting in a recoded sum score for each
survey participant between 0-24 for non-affirmation, 0-12 for healthcare stereotype
threat, and 0-6 for perceived employment inequities. Zero denotes the participant strongly
disagreed with all statements, and the upper range denotes the participant strongly agreed
with all statements.
These linearized index values were then checked to make sure values were not
clustered and hence better represented as a binary outcome. Because each index showed a
wide distribution of answers, simple linear regression was an appropriate way to
determine whether non-affirmation of gender identity was a significant predictor of either
outcome because it compares two quantitative variables, as long as their relationship is
linear and the deviations between the ordinary least-squares regression line and the actual
observed values are homoscedastic and normally distributed.
The research questions and hypotheses guide this study are as follows: RQ1:
What is the relationship between non-affirmation of gender identity and
healthcare stereotype threat?
H01: There is no statistically significant relationship between non-affirmation of
gender identity and healthcare stereotype threat.

50
H11: There is a statistically significant relationship between non-affirmation of
gender identity and healthcare stereotype threat.
RQ2: What is the relationship between non-affirmation of gender identity and
perceived employment inequities?
H02: There is no statistically significant relationship between non-affirmation of
gender identity and perceived employment inequities.
H12: There is a statistically significant relationship between non-affirmation of
gender identity and perceived employment inequities.
The results were interpreted using a P value of <.05 to signify statistical
significance.
Threats to Validity
Internal threats to validity include a low population of TGD identities present in
the study. In the data collection, white cisgender-identified participants are the majority
when it comes to race and gender identity. Sampling bias can be seen in the marketing
and outreach of the survey to a specific population in two ways. The first way is
marketing explicitly to TGD individuals. The second way is marketing to the specific
community of LGBTQ+ persons. External threats in this study are the data from the
study was used to determine whether or not there are statistically significant results for
non-affirmation of gender identity, perceived employment inequities, and healthcare
stereotype threat of the TGD population from the TransPop data set. Recoding of
variables was needed to explain the sum score of the participants in the analysis of the
data set.

51
Ethical Procedures
Collecting data for populations such as the TGD community assists social science
research in improving the lives of TGD people and aiding in additional research
collection that helps to respect the autonomy of the TGD community (Castendea &
Smith, 2022). This study uses principles of the Belmont Report which focuses on the
ethical ideas of respect for persons, beneficence, and justice (Brothers et al., 2019). While
the Belmont Report was drafted to protect research participants, it misses the mark on
protecting minority communities and populations that have been harmed in the past by
the medical community (Friesen et al., 2017). The TGD community has a history of
avoiding medical care due to discrimination and harm creating a culture of violence and a
lack of safety for TGD people.
The IRB must review and approve all research by the researchers of the TransPop
survey and through the Inter-university ICPSR at the University of Michigan. However,
this data set is available publicly with no personal data attached to it. There is no need to
request the TransPop data set.
For this study, the threat of harm is low to none due to the analysis of secondary
data. To ensure the confidentiality of the participants, no data will be collected, and the
data used will remain confidential. The variables include only the sample size and the
demographics of gender, sexual orientation, race, and income keeping other identifiers
out of the analysis. While the original data collected did not contain personal information,
a data breach would not cause harm to those who participated in the study.

52
Furthermore, to protect from a data breach, all information from this study was
protected. Any paper documents will be locked in a secure, fireproof safe. Electronic
materials will be encrypted, and password protected, as well as protected by a VPN
(Virtual Private Network), in my possession at all times. After 7 years after the
completion of this study, all documents, paper and electronic, will be destroyed by ways
of shredding, permanent deletion of files, and reformatting of drives to ensure deletion.
Summary
The purpose of this retrospective, quasi-experimental, quantitative study was to
examine the relationships between non-affirmation of gender identity, healthcare
stereotype threat, and perceived employment inequities for TGD people in healthcare
organizations. The variables measured in this study using secondary data are obtained
from the TransPop Survey from the Inter-university ICPSR at the University of Michigan
website. A correlation analysis will be used to analyze data from the TransPop data set
using SPSS for Windows Version 29. Section 3 will display the results and findings of the
analysis of the TransPop data set.
Section 3: Presentation of the Results and Findings
Introduction
The purpose of this quantitative retrospective quasi-experimental study was to
examine whether there is a relationship between the non-affirmation of gender identity,
healthcare stereotype threat, and perceived employment inequities concerning employees
in healthcare systems and organizations. This section includes the data collection of the
data set, the results from the analysis, and the summary.

53
The research questions and hypotheses guide this study are as follows: RQ1:
What is the relationship between non-affirmation of gender identity and
healthcare stereotype threat?
H01: There is no statistically significant relationship between non-affirmation of
gender identity and healthcare stereotype threat.
H11: There is a statistically significant relationship between non-affirmation of
gender identity and healthcare stereotype threat.
RQ2: What is the relationship between non-affirmation of gender identity and
perceived employment inequities?
H02: There is no statistically significant relationship between non-affirmation of
gender identity and perceived employment inequities.
H12: There is a statistically significant relationship between non-affirmation of
gender identity and perceived employment inequities.
Data Collection of Secondary Data Set
The secondary data set was collected from the TransPop study (Meyer, 2021).
The data was pulled from the Excel document and SPSS data set from the Inter-university
ICPSR at the University of Michigan There were no discrepancies in the use of the
secondary data set from the plan presented previously in Section 2.
The focus of the study was on a random sample of TGD employees throughout
the US in 2016-2018. Recruitment and screening were performed by Gallup Inc. using
two methods. First, US Adults using random digit dialing on cell and landline phones
were contacted and asked if they identified as lesbian, gay, bisexual, or transgender. Then,

54
it shifted to address-based sampling by mail or online survey where Gallup sent out
surveys based on address. The total survey sample in both cisgender and TGD identities
over the age of 18 years old. The baseline descriptive and demographic characteristics of
the sample included age, gender identity, sexual orientation, race, and education.
The statistical assessment used to assess the hypotheses for each of the research
questions proposed was a simple linear regression of the variables. Simple linear
regression was chosen as an appropriate method to assess whether non-affirmation of
gender identity significantly predicted either outcome variable while adhering to the
statistical assumptions. Because the one outcome and one predictor variable all showed a
wide distribution of answers, it compared two quantitative variables, as long as their
relationship is linear and the deviations between the ordinary least-squares regression line
and the actual observed values are homoscedastic and normally distributed.
The procedures used to account for this analysis were due to the multiple factors
influencing healthcare stereotype threat and perceived employment inequities. There was
no basic univariate analysis, covariates, or confounding variables. Using SPSS, the
analyze option was used to review descriptive statistics and frequencies to create tables in
the software.
For gender identity, Tran woman or male-to-female (MTF) made up 43.2 % (115
individuals) with Trans man or female-to-male (FTM) at 28.6 % (76 individuals) and
Trans GNB or transgender non-binary at 28.2% (75 individuals; Table 1). The mean age
of respondents was 39 years old with the highest numbers identifying as heterosexual
55
(21.7%), bisexual (19.0%), and queer (18.3%; Table 1). In total, 73.2% of respondents
identify as White, 9.6% as Hispanic, 8.8% as Black, 4.2% as Asian, and 4.2% as Other
(Table 1).
Table 1
TransPop Demographics
Gender N Percent
Trans man (FTM)
76
28.6
Trans woman (MTF)
115
43.2
Trans GNB
75
28.2
Total
266
100.00
Age
N
266
Mean
39.3
Median
34
Std. deviation
16.9
Minimum
18
Maximum
72
Sexual identity
Frequency
Percent
Straight/heterosexual
57
21.7
Lesbian
23
8.7
Gay
22
8.4
Bisexual
50
19.0
Queer
48
18.3
Same gender loving
9
3.4
Other
21
8.0
56
Asexual spectrum
12
4.6
Pansexual
21
8.0
Total
263
100.00
Race
Frequency
Percent
White
191
73.2
Other
11
4.2
Black
23
8.8
Asian
11
4.2
Hispanic
25
9.6
Total 261 100.0
Note. Demographics of the participants in the TransPop study who identified only as
transgender and gender diverse.
Results
Descriptive statistics and related data visualizations were reviewed for the
variables included in RQ1 and RQ2 using SPSS analysis output. The sample included a
total of n=1436 samples; n=1162 were cisgender male and female and n=274 TGD
individuals. Of the 274 TGD individuals, 266 were found to be valid (i.e., had complete
data) for the data analysis (Table 1). Three new variables were created for the analyses,
described as follows.
Table 2 refers to the TransPop survey questions that contain data for the variable
of non-affirmation of gender identity. Participants were given six statements using a
5point Likert scale in which they had to state whether they “strongly disagreed,
disagreed, neither agree nor disagree, agreed, or strongly agreed” to the statements. The
original dataset used 1 for “strongly disagree,” 2 for “disagree,” 3 for “neither agree nor

57
disagree,” 4 for “agree,” and 5 for “strongly agree.” Scores were recoded to range from 0
to 4, then added together for a single index, resulting in a recoded sum score for each
survey participant between 0-24. Zero denotes the participant has the least affirmation
and 24 denotes the participant has a strong affirmation of their gender identity. Strong
affirmation means that the TGD person felt affirmed in their gender identity, gender
expression, pronouns were respected, could “pass” regarding the gender identity, and
whether they felt understood as a person.
Table 2
Nonaffirmation of Gender Identity Statements
Strongly
Disagree
Disagree
Neither
Agree or
Disagree
Agree
Strongly
Agree
Total
I have to repeatedly
explain my gender
identity to people or
correct the pronoun.
59
(22.2%)
49
(18.4%)
49
(18.4%)
63
(23.7%)
46
(17.3%)
266
(100%)
I have difficulty being
perceived as my
gender.
68
(25.6%)
40
(15.0%)
43
(16.2%)
61
(22.9%)
54
(20.3%)
266
(100%)
I have to work hard
for people to see my
gender accurately.
61
(22.9%)
45
(16.9%)
39
(14.7%)
60
(22.6%)
61
(22.9%)
266
(100%)
I have to be overly
masculine or overly
feminine in order for
people to accept my
gender.
61
(22.9%)
51
(19.2%)
51
(19.2%)
64
(24.1%)
39
(14.7%)
266
(100%)
People don't respect
my gender identity
because of my
appearance or body.
62
(23.3%)
48
(18.0%)
51
(19.2%)
53
(19.9%)
52
(19.5%)
266
(100%)

58
People don't
understand me
because they don't see
my gender as I do.
45
(16.9%)
43
(16.2%)
36
(13.5%)
77
(28.9%)
65
(24.4%)
266
(100%)
Note. Questions participants were asked about the affirmation of their gender identity.
Verification of the six questions used in the construction of the index variable for
non-affirmation of gender identity do not suffer from multicollinearity, as indicated by
Variance Inflation Factors (VIFs) less than five. Table 3 shows the results of this test.
Table 3
VIF Table for Nonaffirmation of Gender Identity
Non -affirmation of gender identity
VIF
I have to repeatedly explain my gender identity to people or correct the
pronoun
2.09
I have difficulty being perceived as my gender.
4.94
I have to work hard for people to see my gender accurately.
4.11
I have to be overly masculine or overly feminine in order for people to accept
my gender.
2.14
People don't respect my gender identity because of my appearance or body.
4.05
People don't understand me because they don't see my gender as I do.
3.03
Note: VIF less than 5
Figure 3 shows that although many respondents reported no incidents of
nonaffirmation of gender identity, the remainder of the distribution is relatively
uniform.
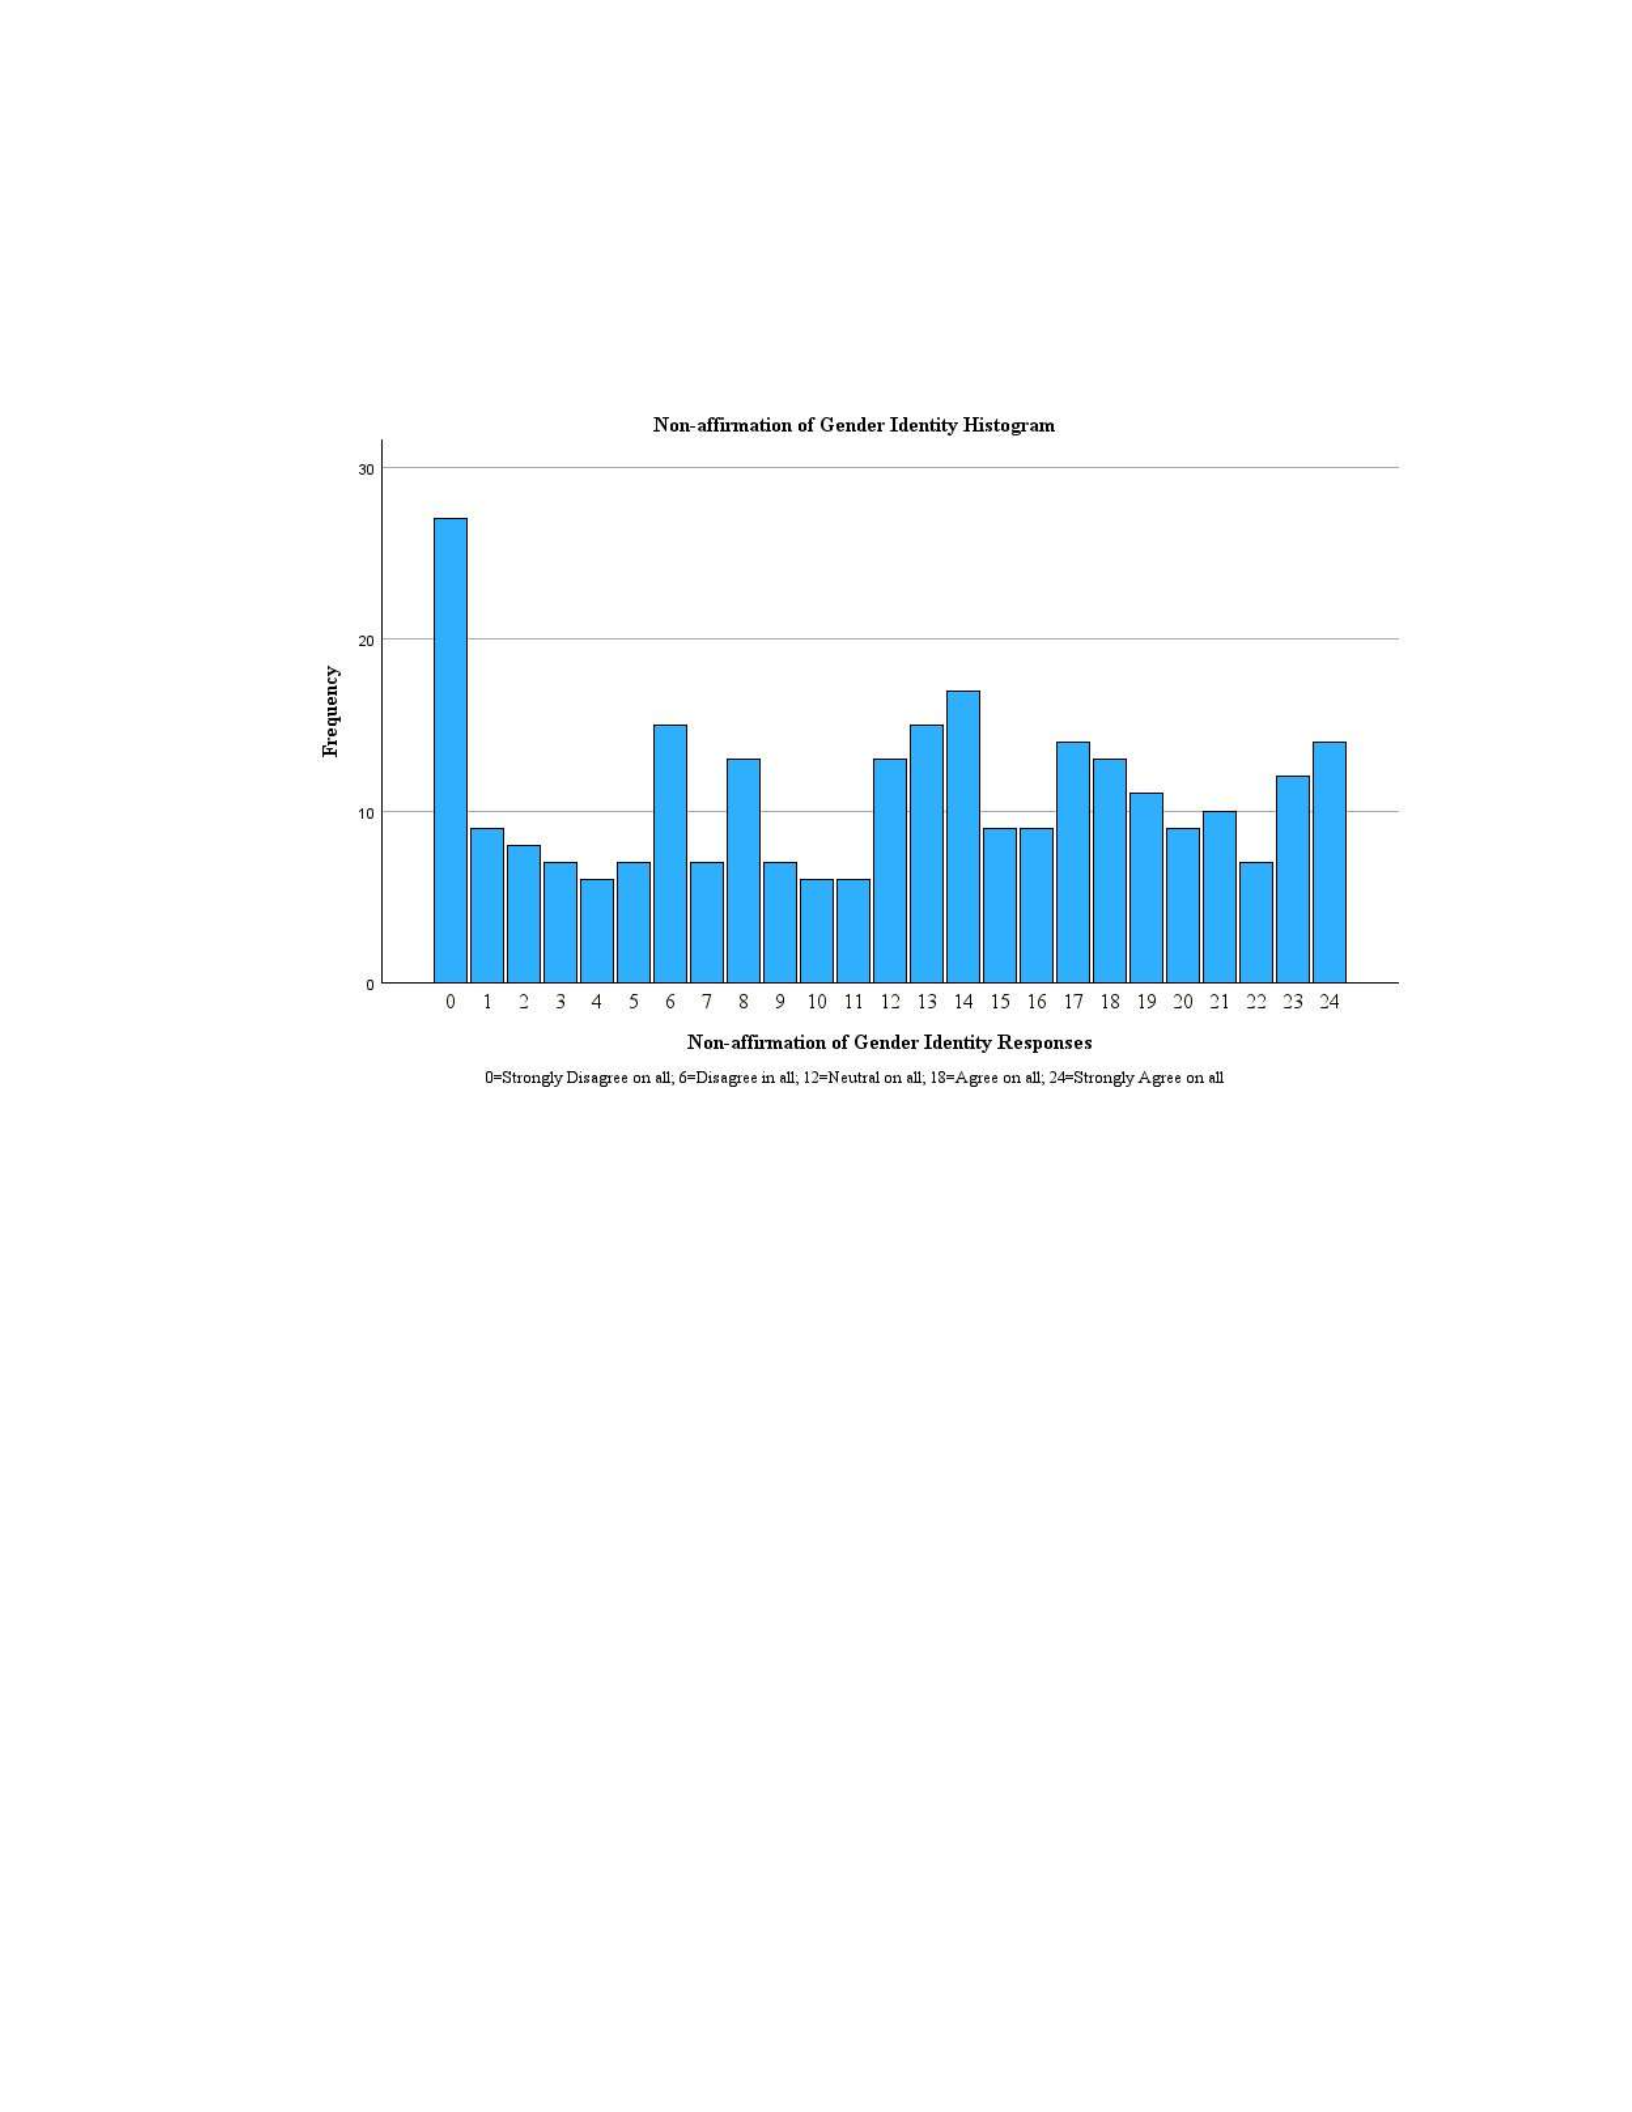
59
Figure 3
Frequencies of Nonaffirmation of Gender Identity
Table 4 refers to the variable of healthcare stereotype threat. Participants were
given four statements using a 5-point Likert scale in which they had to state whether they
“strongly disagreed, disagreed, neither agree nor disagree, agreed, or strongly agreed” to
the statements. The original data set used 1 for “strongly disagree,” 2 for “disagree,” 3 for
“neither agree nor disagree,” 4 for “agree,” and 5 for “strongly agree.” Scores were
recoded to range from 0 to 4, then added together for a single index, resulting in a
recoded sum score for each survey participant between 0-16. Zero denotes the participant
with the least healthcare stereotype threat, and 16 means strong healthcare stereotype
threat. Strong healthcare stereotype means the TGD patient felt judged negatively,

60
worried about negative health interactions, receives a negative diagnosis when seeing a
provider, and is a negative stereotype for the TGD community.
Table 4
Healthcare Stereotype Threat Statements
Strongly
Disagree
Disagree
Neither
Agree or
Disagree
Agree
Strongly
Agree
Total
When seeking
healthcare, I worry
about being
negatively judged
because of my gender
identity or sexual
orientation.
31
(11.7%)
39
(14.7%)
35
(13.2%)
91
(34.2%)
70
(26.3%)
266
(100%)
When seeking
healthcare, I worry
that evaluations of
me may be
negatively affected
by my gender
identity or sexual
orientation.
30
(11.3%)
41
(15.4%)
38
(14.3%)
94
(35.3%)
63
(23.7%)
266
(100%)
When seeking
healthcare, I worry
that diagnoses of
me/my health may be
negatively affected
by my gender
identity or sexual
orientation.
31
(11.7%)
48
(18.0%)
47
(17.7%)
79
(29.7%)
61
(22.9%)
266
(100%)
When seeking
healthcare, I worry
that I might confirm
negative stereotypes
about LGBT people.
62
(23.3%)
60
(22.6%)
43
(16.2%)
60
(22.6%)
41
(15.4%)
266
(100%)
Note. Questions participants were asked about when seeking healthcare.
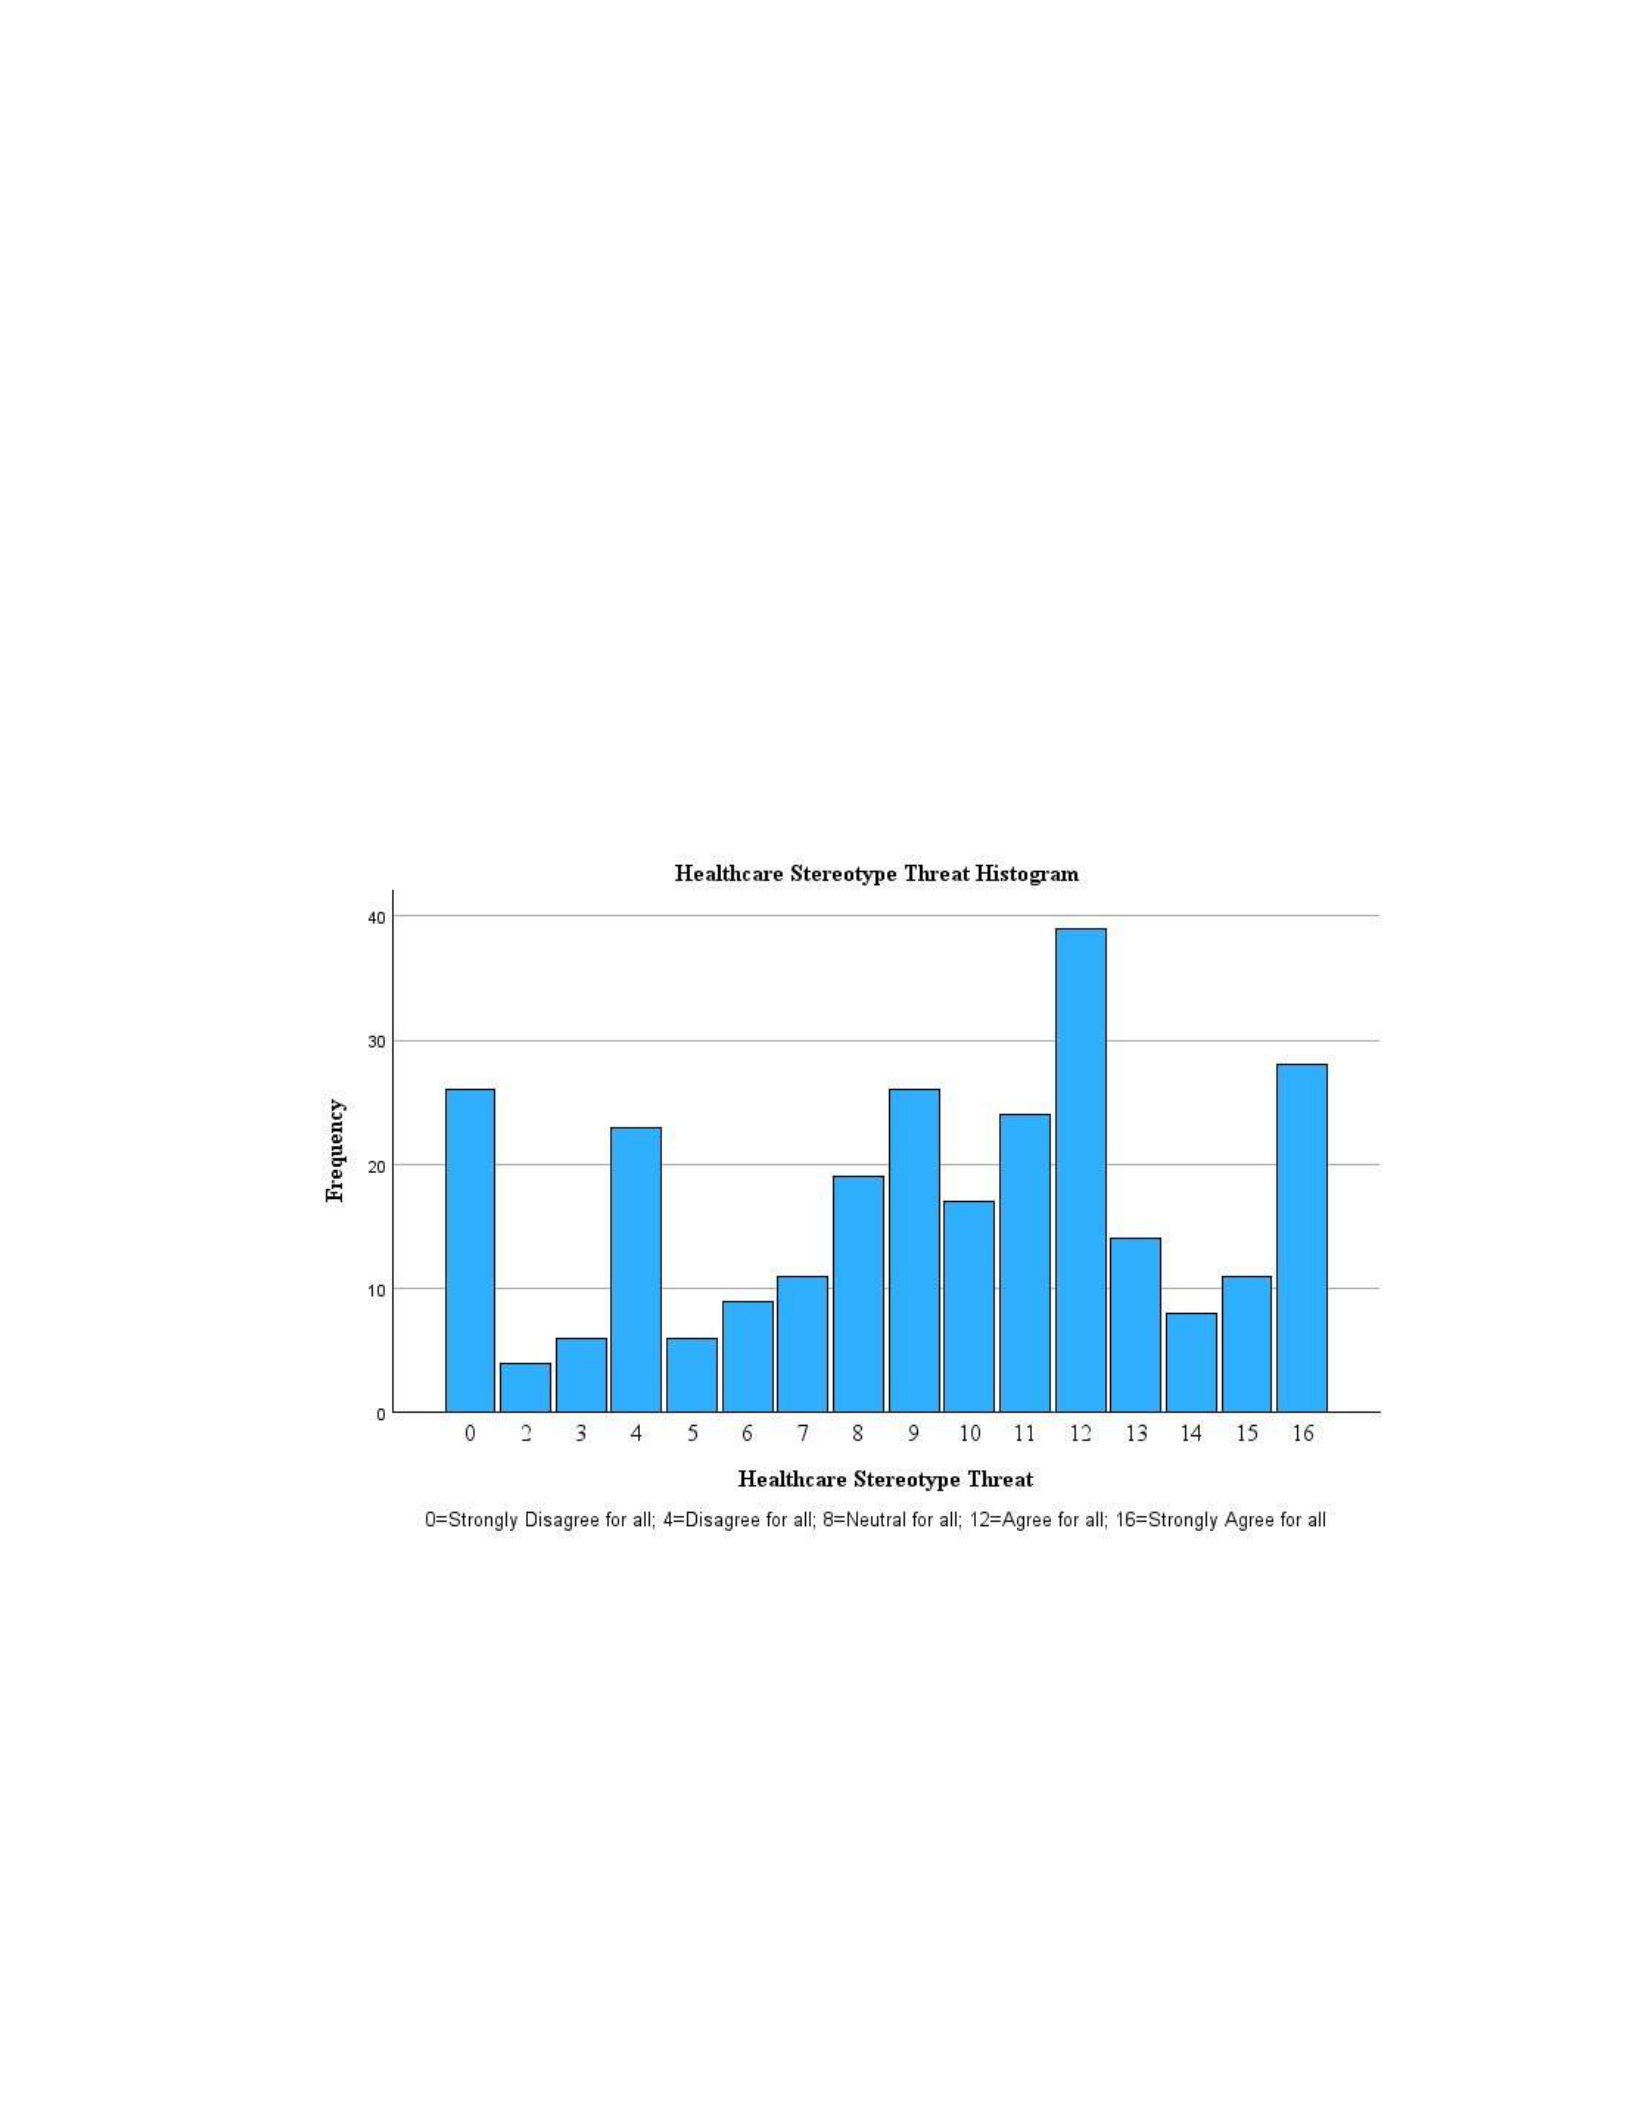
61
Figure 4 shows the distribution of healthcare stereotype threat shows a peak
around 12, with many people reporting either no threat or maximum threat. The
participants in the 0 and 16 categories were those that answered every stereotype threat
question the same, with either “Strongly disagree” or “Strongly agree” on all four
questions.
Figure 4
Frequencies of Healthcare Stereotype Threat
Table 5 refers to the variable of perceived employment inequities. Participants
were asked about their employment status on how often the employee was fired from
their job, denied a job, denied a promotion, or received a negative evaluation based on
their perception. The scale used for these statements is how often the employee was fired,

62
denied a job or promotion, or received a negative evaluation with 1 being “never,” 2
being “once,” 3 being “twice,” and 4 being “three or more times.” Scores were recoded to
range from 0 to 4, then added together for a single index, resulting in a recoded sum score
between 0-8. Zero denotes the participant had no employment issues, and 6 means three
or more issues such as termination, being denied a job or promotion, or receiving
negative evaluations. The two variables being used to measure negative employment
outcomes record the number of times fired, demoted, etc. as 0, 1, 2, or 3 or more. Even
though there is no true count for people fired more than three times, these represent a
relatively small portion of the sample (around 10%). The survey questions will be treated
as quantitative variables by simply adding the two questions of how often the employee
was denied a job or promotion, negative feedback, or fired to get a rough measure of
negative employment outcomes.
Table 5
Perceived Employment Inequity Statements
Never
Once
Twice
Three or
more
Total
Since the age of 18, how often
were you fired from your job or
denied a job?
127
(47.7%)
40
(15.0%)
35
(13.2%)
64
(24.1%)
266
(100%)
Since the age of 18, how often
were you denied a promotion or
received a negative evaluation?
142
(53.4%)
50
(18.8%)
29
(10.9%)
45
(16.9%)
266
(100%)
Note. Questions participants were asked about their employment.
Figure 5 shows that although many respondents reported no perceived
employment inequities, the remainder of the distribution is relatively uniform.
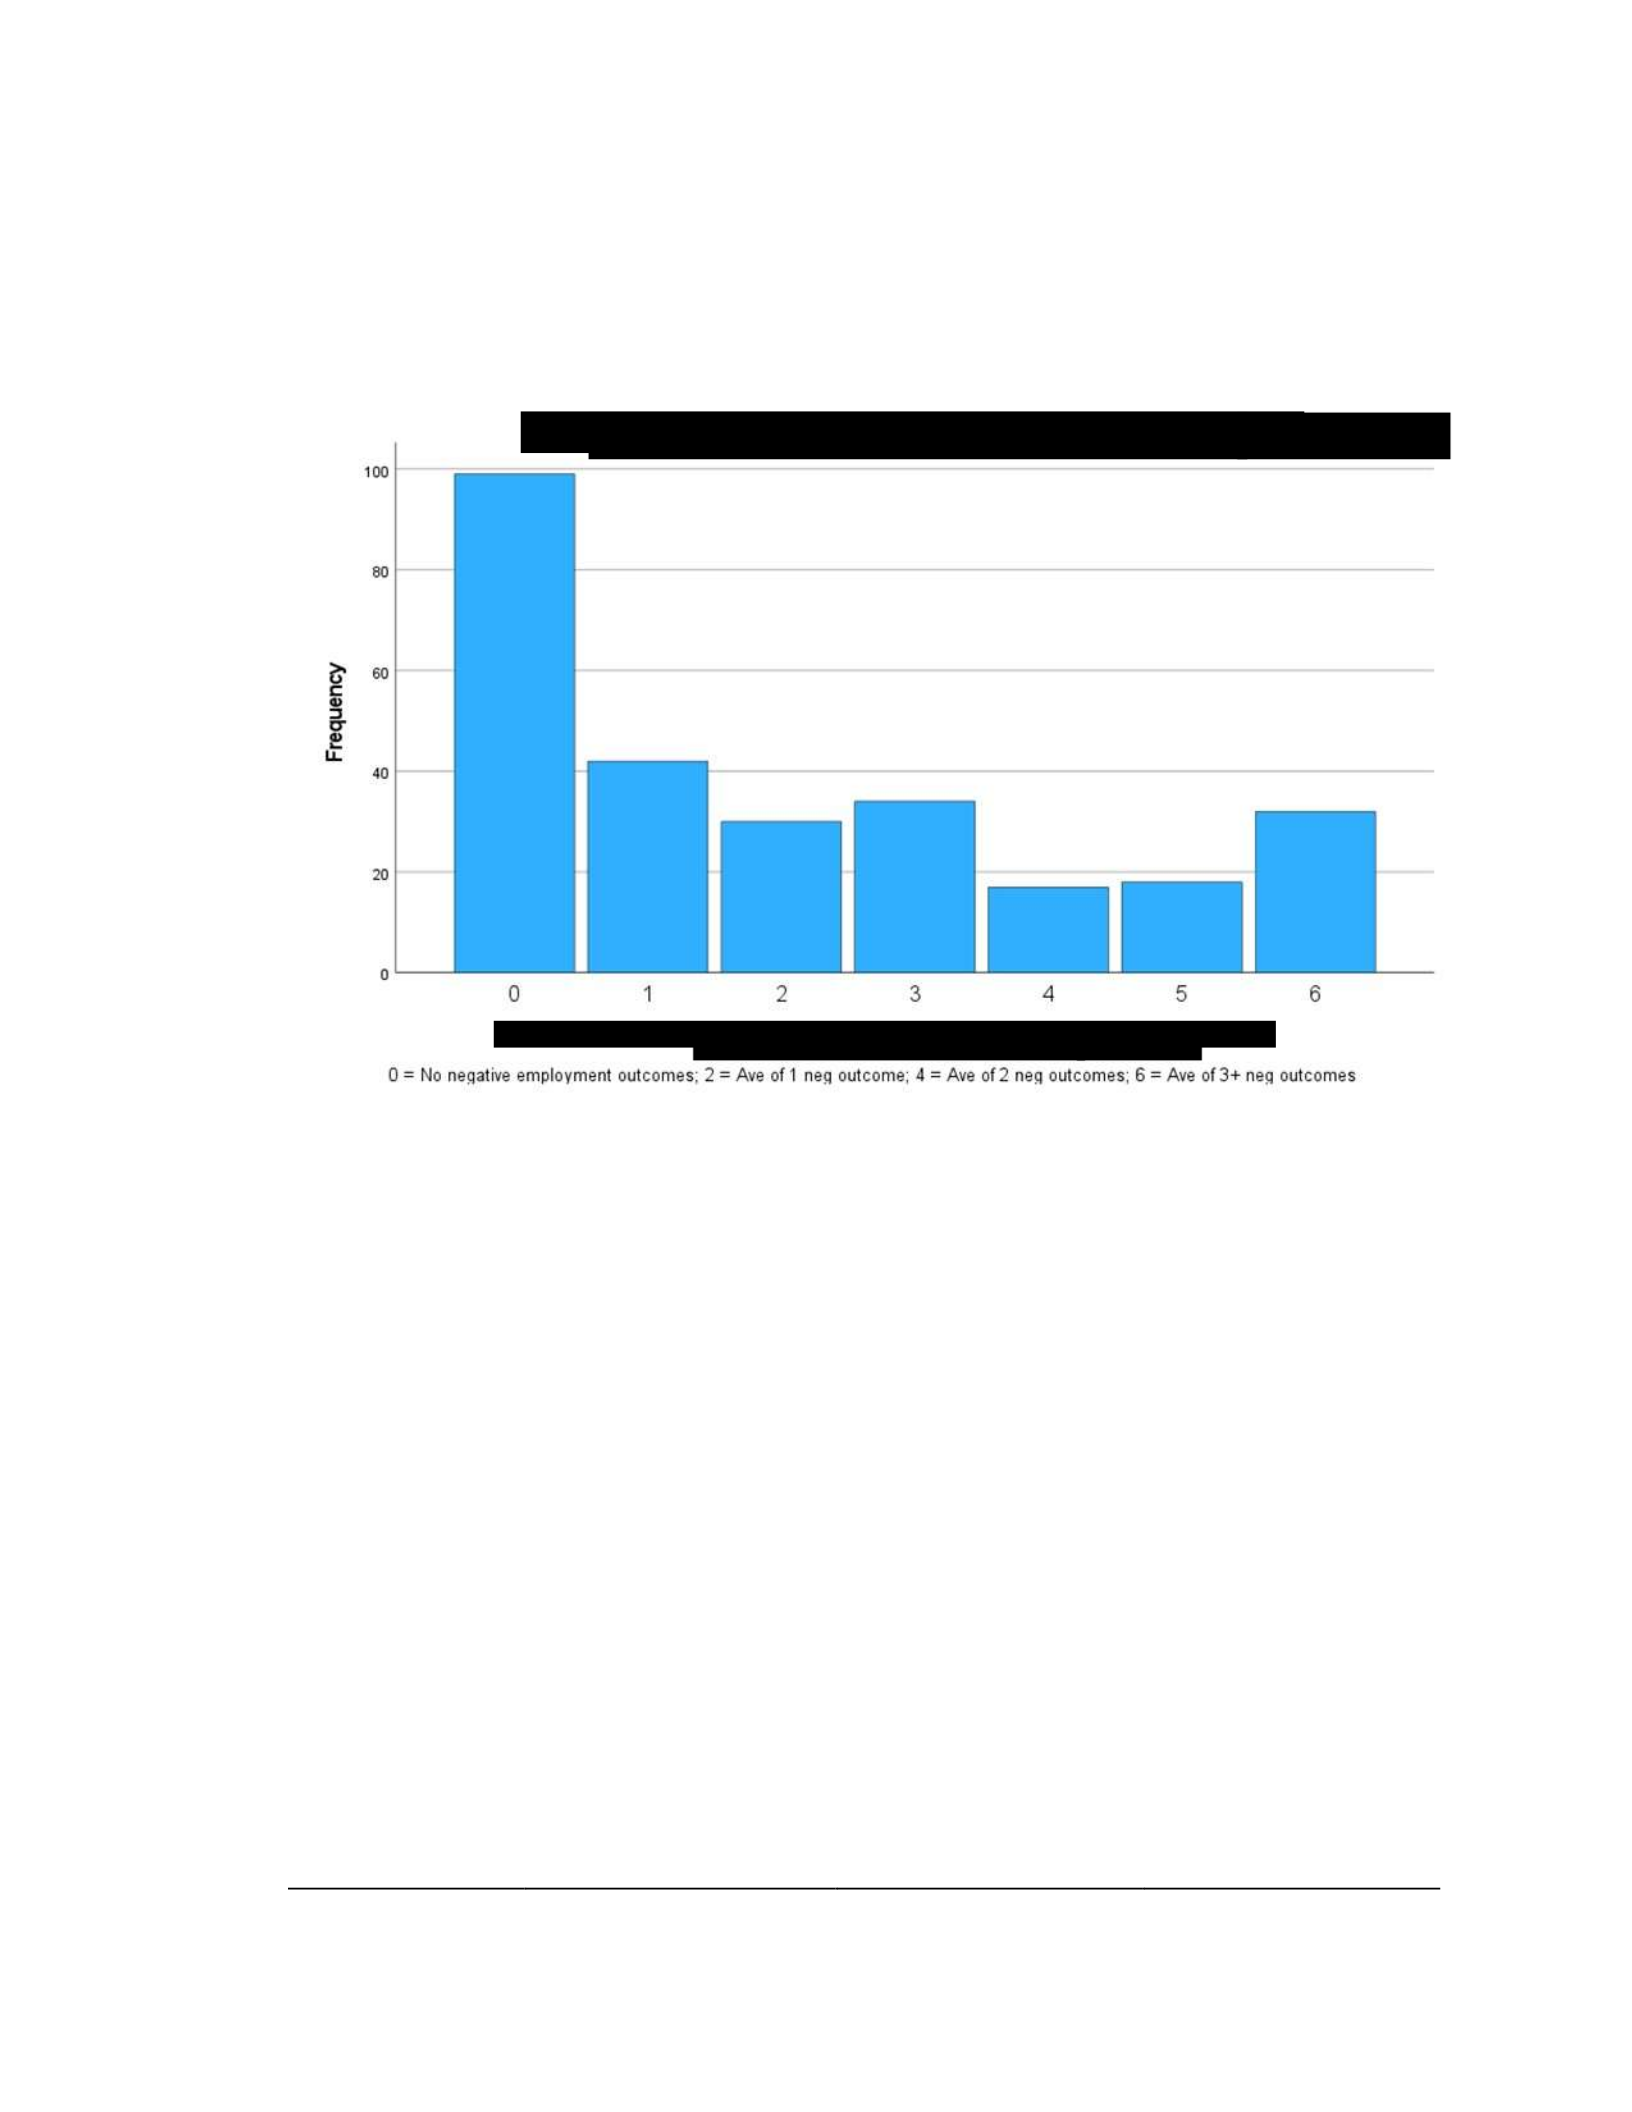
63
Figure 5
Frequencies of Perceived Employment Inequities
Table 6 shows the sample size for analyses is 266 since all models include
nonaffirmation of gender identity as the main predictor. The average index for perceived
employment inequities is 2, with a median of 1, indicating that values are right skewed.
Index values range from 0 to 6. Healthcare stereotype threat and non-affirmation of
gender identity have means of 9.1 and 12.1, respectively, on scales from 0 to 16 and 24,
respectively. Standard deviations are relatively large given the means, indicating that
there is significant variation in participant responses.
Table 6
Average Respondent Experience of Variables
Histogram of Perceived Employment Inequities
Perceived Employment Inequities

64
Non-affirmation of Healthcare stereotype Perceived gender identity
threat employment
inequities
N
266
266
266
Mean
12.1
9.1
2.0
Median
13
10
1
Std. deviation
7.5
4.7
2.1
Minimum
0
0
0
Maximum
24
16
6
Note: Average respondent experiencing one such event of each variable.
Both research questions use simple linear regression analysis. The four
assumptions for simple linear regression are (1) a linear relationship between the
independent and dependent variables; (2) no non-linear pattern exists in the residuals
relative to any independent variable; (3) homoscedasticity through which the residuals
have constant variance at every point relative to any independent variable; and (4) the
residuals in the model exhibit multivariate normality.
RQ1: What is the Relationship Between Non-Affirmation of Gender Identity and
Healthcare Stereotype Threat?
Assumption 1
The first assumption of a simple linear regression is that the relationship between
the predictor and the outcome is linear. Therefore, for the first assumption, I needed to
check to make sure the relationships between non-affirmation of gender identity and
healthcare stereotype threat are best described by a straight rather than curved line.
The scatterplot of healthcare stereotype threat as a function of non-affirmation of
gender identity (Figure 6) shows a weak linear relationship that is increasing.
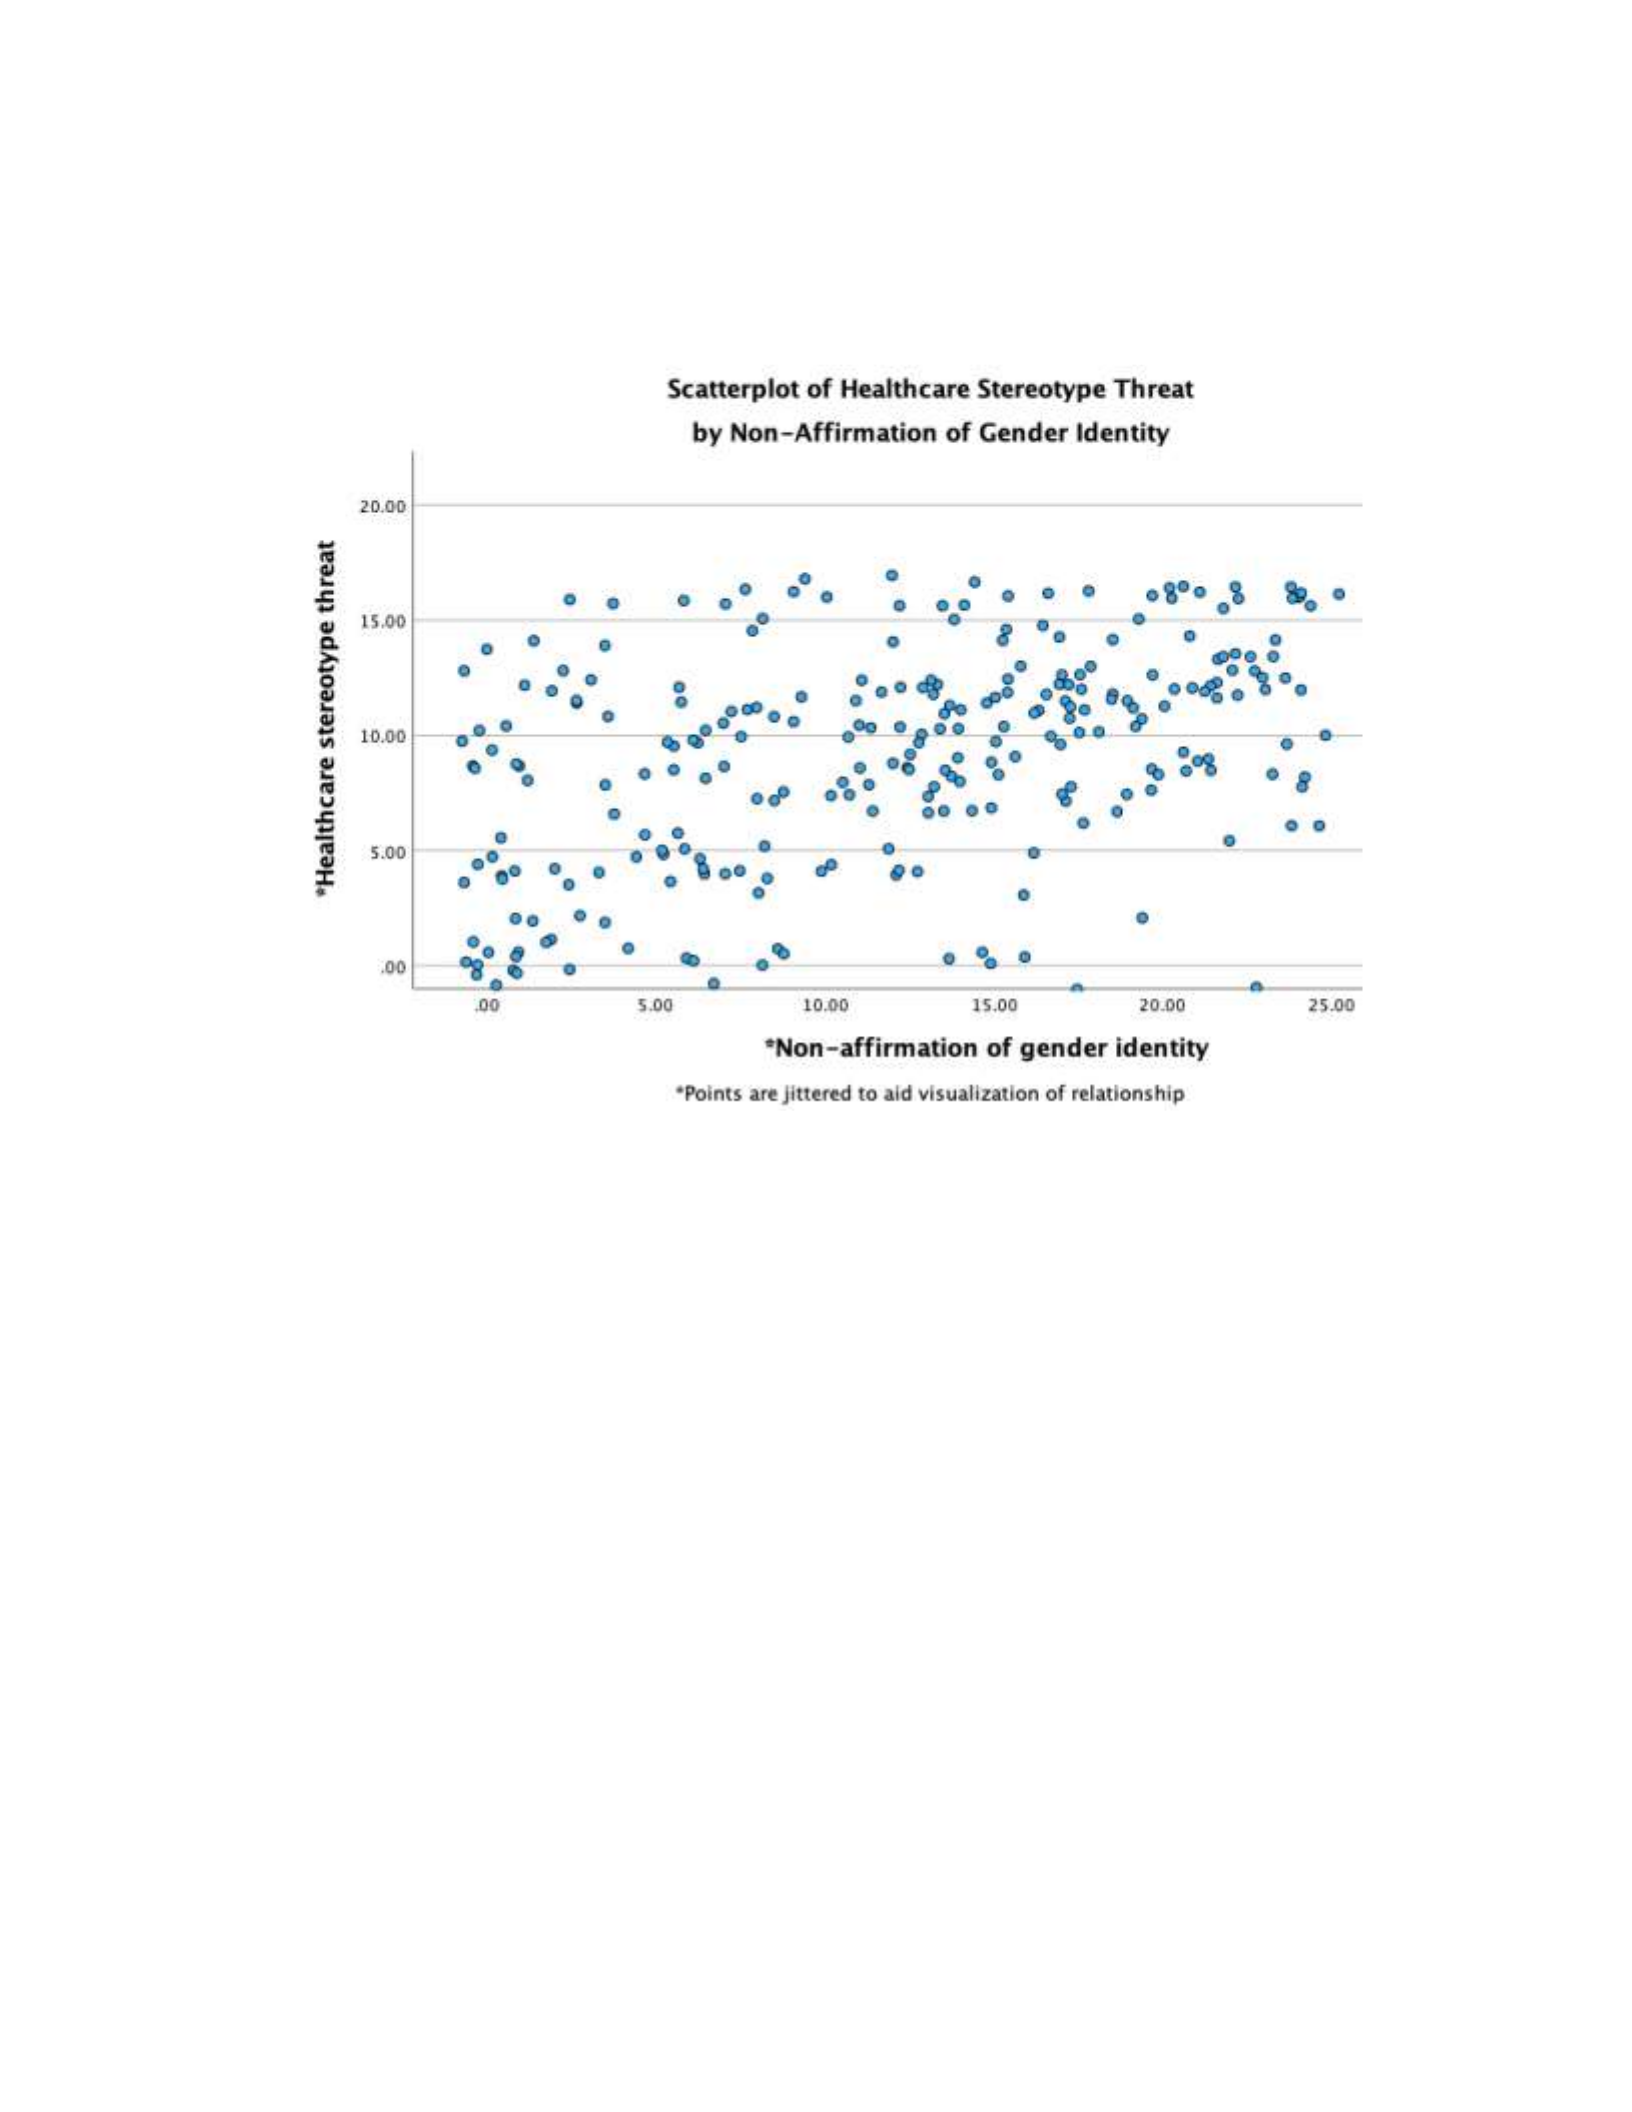
65
Figure 6
Scatterplot for Nonaffirmation of Gender Identity and Healthcare Stereotype Threat
Assumption 2
The second assumption states that the relationship between the predictor and the
errors should not show any curved pattern. Because the mean of the errors is zero by
construction, the correlation between the predictors and the residuals will always be zero.
But the relationship can still be curved if the model over- or under-estimates the outcome
for low values of the predictor but not for high values, or not for medium values.
Assumptions 3
The third assumption states that the relationship between each predictor and the
errors should be homoscedastic, meaning the error terms are of similar magnitude
regardless of the value of the predictor. Homoscedasticity is visually checked by looking

66
for a funnel shape to residuals, which would suggest that the model does a better job for
low values of the predictor than for high values, or vice versa.
Both of these assumptions can also be checked in the scatterplot shown in Figure
6 because the error terms are based on only one predictor. Therefore, if there is no curved
relationship between non-affirmation of gender identity and healthcare stereotype threat,
there will also be no curved relationship between non-affirmation of gender identity and
the error terms. Likewise, there is no funnel shape to the points shown in the scatterplot in
Figure 6, which indicates homoskedasticity. Hence, Assumptions 2 and 3 are satisfied.
Assumption 4
The fourth assumption is that the residuals show normality. This is shown through
a P-P or Q-Q plot, which shows the observed error terms, ordered from most negative to
most positive, compared to the expected values of error terms if they are normally
distributed. We visually inspect how close the points are to a straight line, which indicates
perfect normality. The P-P plot shows cumulative probabilities and is hence more
sensitive to deviations from normality in the center of the distribution. The Q-Q plot
shows quantiles and is hence more sensitive to deviations in the tails.
Both plots for the model predicting healthcare stereotype threat (Figure 7) indicate
that the residuals are normally distributed, shown by the adherence of the expected
normal distribution of the residuals to the observed errors.
Figure 7
Normal P-P and Q-Q Plots of Residuals—Healthcare Stereotype Threat
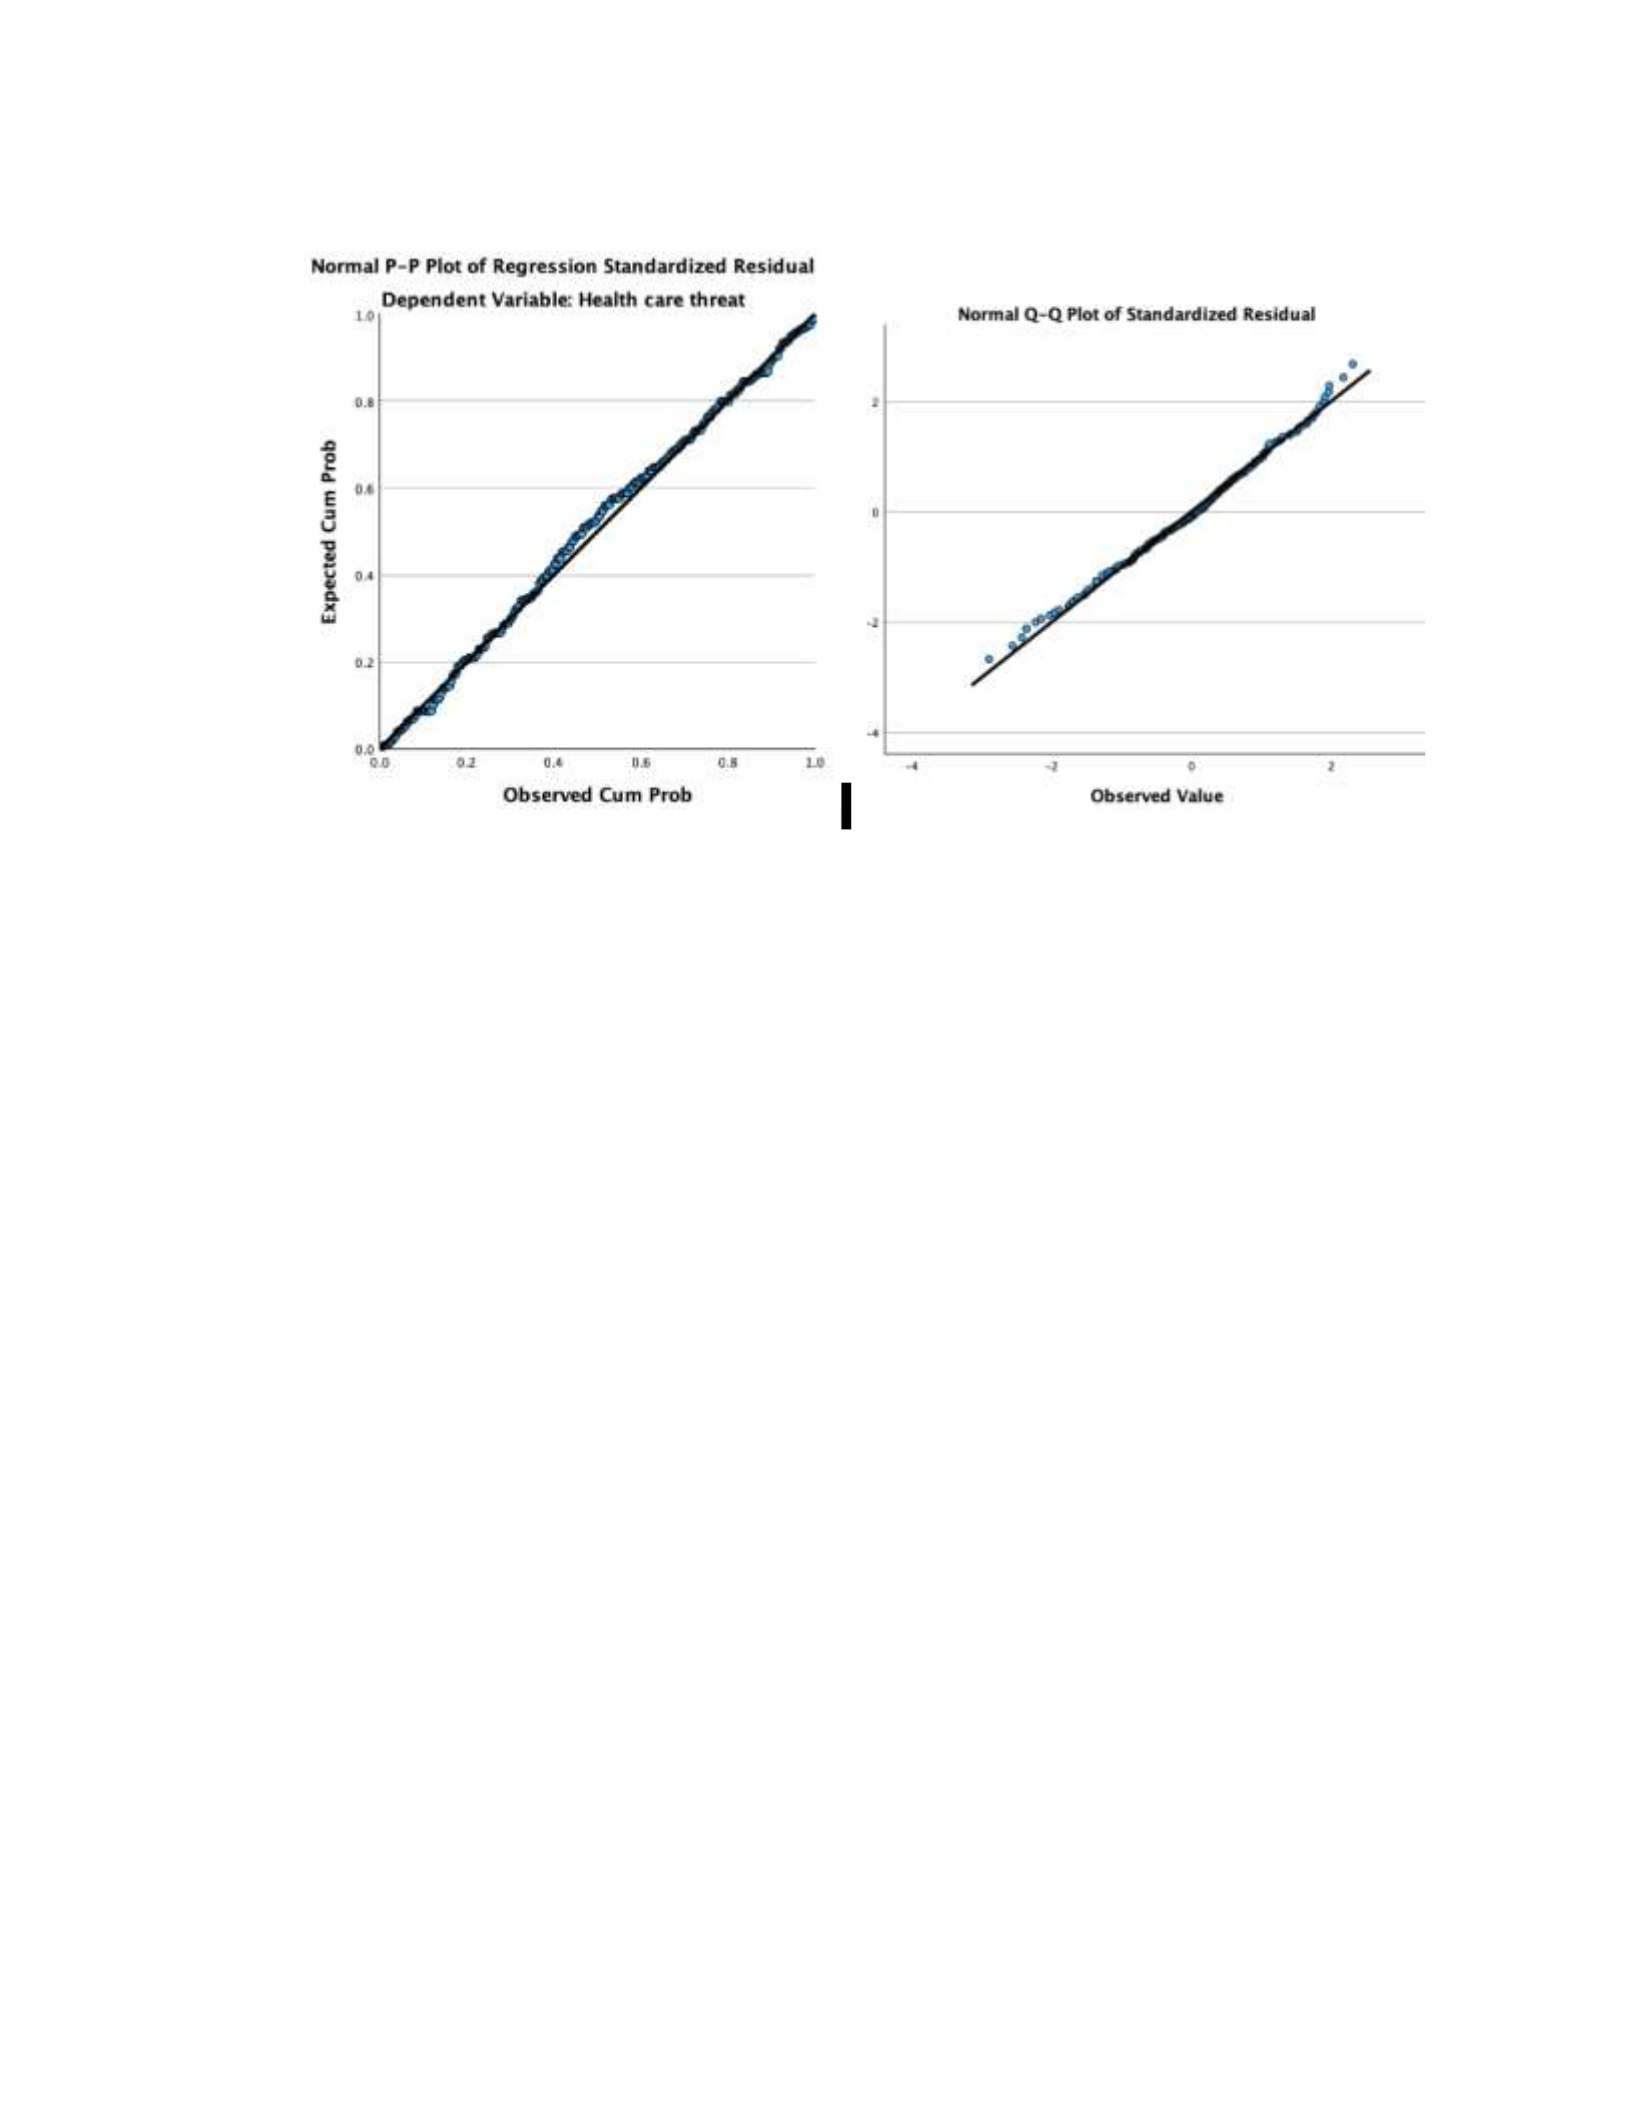
67
Note: Figures show the straight line for normality of residuals of the independent
and dependent variables.
To approach RQ1 (What is the relationship between non-affirmation of gender
identity and healthcare stereotype threat?), a simple linear regression analysis was
conducted to evaluate the prediction of healthcare stereotype threat from non-affirmation
of gender identity. The results of the linear regression analysis (Table 7-9) revealed
nonaffirmation of gender identity to be a statistically significant predictor of the model (p
<
.001), shown in Table 9. The regression coefficient [B = .281, 95% C.I. (.213, .349), p <
.001] associated with non-affirmation of gender identity suggests that with each
additional point on the 24-point composite scale (Table 2) indicating non-affirmation of
gender identity, the healthcare stereotype threat increases by approximately 0.287 units
on the composite scale ranging from 0 to 16 units (Table 4).
The R2 value of .496 (Table 7) associated with this regression model suggests that
the non-affirmation of gender identity accounts for 49.9% of the variation in healthcare
68
stereotype threat, which means that 50.1% of the variation cannot be explained by
nonaffirmation of gender identity alone. Based on these results, the null hypothesis, that
there is no association between the degree of non-affirmation of gender identity and
healthcare stereotype threat, can be rejected. This is support for the alternative hypothesis
that the intensity of non-affirmation of gender identity one experiences increases the
likelihood of healthcare stereotype threat.
Table 7
Model Summary for Nonaffirmation of Gender Identity and Healthcare Stereotype Threat
Model Summarya
Model
R
R Square
Adjusted R
square
Std. error of the
estimate
1
.499a
.202
.199
4.21281
a. Predictors: (Constant); Non-affirmation of gender identity
b. Dependent Variable: Healthcare stereotype threat
Table 8 shows that the model proposed predicting healthcare stereotype threat as a
function of non-affirmation of gender identity performs statistically significantly better
than the null model, which simply estimates healthcare threat as the sample mean (F =
66.642, p-value < .001).
Table 8
ANOVA Test for Nonaffirmation of Gender Identity and Healthcare Stereotype Threat
ANOVAa
Model
Sum of
squares
df
Mean
square
F
Sig.
1
Regression
1182.750
1
1182.750
66.642
<.001b
Residual
4685.400
264
17.748
Total
5868.150
265
69
a. Dependent Variable: Healthcare stereotype threat
b. Predictors: (Constant); Non-affirmation of gender identity
Table 9 shows the average index for healthcare stereotype threat is 5.72. All else
equal, for each additional point of increase in the non-affirmation of gender identity
experienced by trans participants in the survey, health care stereotype threat increases by
0.281 points (t = 8.163, p-value < .001).
Table 9
Coefficients for Nonaffirmation of Gender Identity and Healthcare Stereotype Threat
Coefficientsa
Unstandardized
B
Coefficients
std. error
Standardized
coefficients
beta
t
Sig.
(Constant)
5.72
.490
11.673
<.001
Non-affirmation of
gender identity
.281
.034
.449
8.163
<.001
a. Dependent Variable: Perceived employment inequities
RQ2: What is the Relationship Between Non-Affirmation of Gender Identity and
Perceived Employment Inequities?
Assumption 1
The first assumption of a simple linear regression is that the relationship between
the predictor and the outcome is linear. Therefore, for the first assumption, I needed to
check to make sure the relationships between non-affirmation of gender identity and
perceived employment inequities are best described by a straight rather than curved line.

70
The scatterplot of perceived employment inequities as a function of
nonaffirmation of gender identity shows no relationship, linear or otherwise (Figure 8).
The first assumption is satisfied because the relationship is not of a higher order.

71
Figure 8
Scatterplot of Nonaffirmation of Gender Identity and Perceived Employment Inequities
Assumption 2
The second assumption states that the relationship between the predictor and the
errors should not show any curved pattern. Because the mean of the errors is zero by
construction, the correlation between the predictors and the residuals will always be zero.
But the relationship can still be curved if the model over- or under-estimates the outcome
for low values of the predictor but not for high values, or not for medium values.
Assumptions 3
The third assumption states that the relationship between each predictor and the
errors should be homoscedastic, meaning the error terms are of similar magnitude
regardless of the value of the predictor. Homoscedasticity is visually checked by looking

72
for a funnel shape to residuals, which would suggest that the model does a better job for
low values of the predictor than for high values, or vice versa.
Both assumptions can also be checked in the scatterplot shown in Figure 8
because the error terms are based on only one predictor. Therefore, if there is no curved
relationship between non-affirmation of gender identity and perceived employment
inequities, there will also be no curved relationship between non-affirmation of gender
identity and the error terms. Likewise, there is no funnel shape to the points shown in the
scatterplot in Figure 8, which indicates homoskedasticity. Hence, Assumptions 2 and 3
are satisfied.
Assumption 4
The fourth assumption is that the residuals show normality. This is shown through
a P-P or Q-Q plot, which shows the observed error terms, ordered from most negative to
most positive, compared to the expected values of error terms if they are normally
distributed. I visually inspected how close the points are to a straight line, which indicates
perfect normality. The P-P plot shows cumulative probabilities and is hence more
sensitive to deviations from normality in the center of the distribution. The Q-Q plot
shows quantiles and is hence more sensitive to deviations in the tails.
Both plots (Figure 9) for the model predicting perceived employment inequities
indicate that the residuals are leptokurtic, meaning that the error terms are more narrowly
distributed around zero than would be expected in a normal distribution. Despite this
deviation from the expectation, linear regression is fairly robust to violations of the fourth
assumption, provided that the first three assumptions hold (Freedman, 2005).
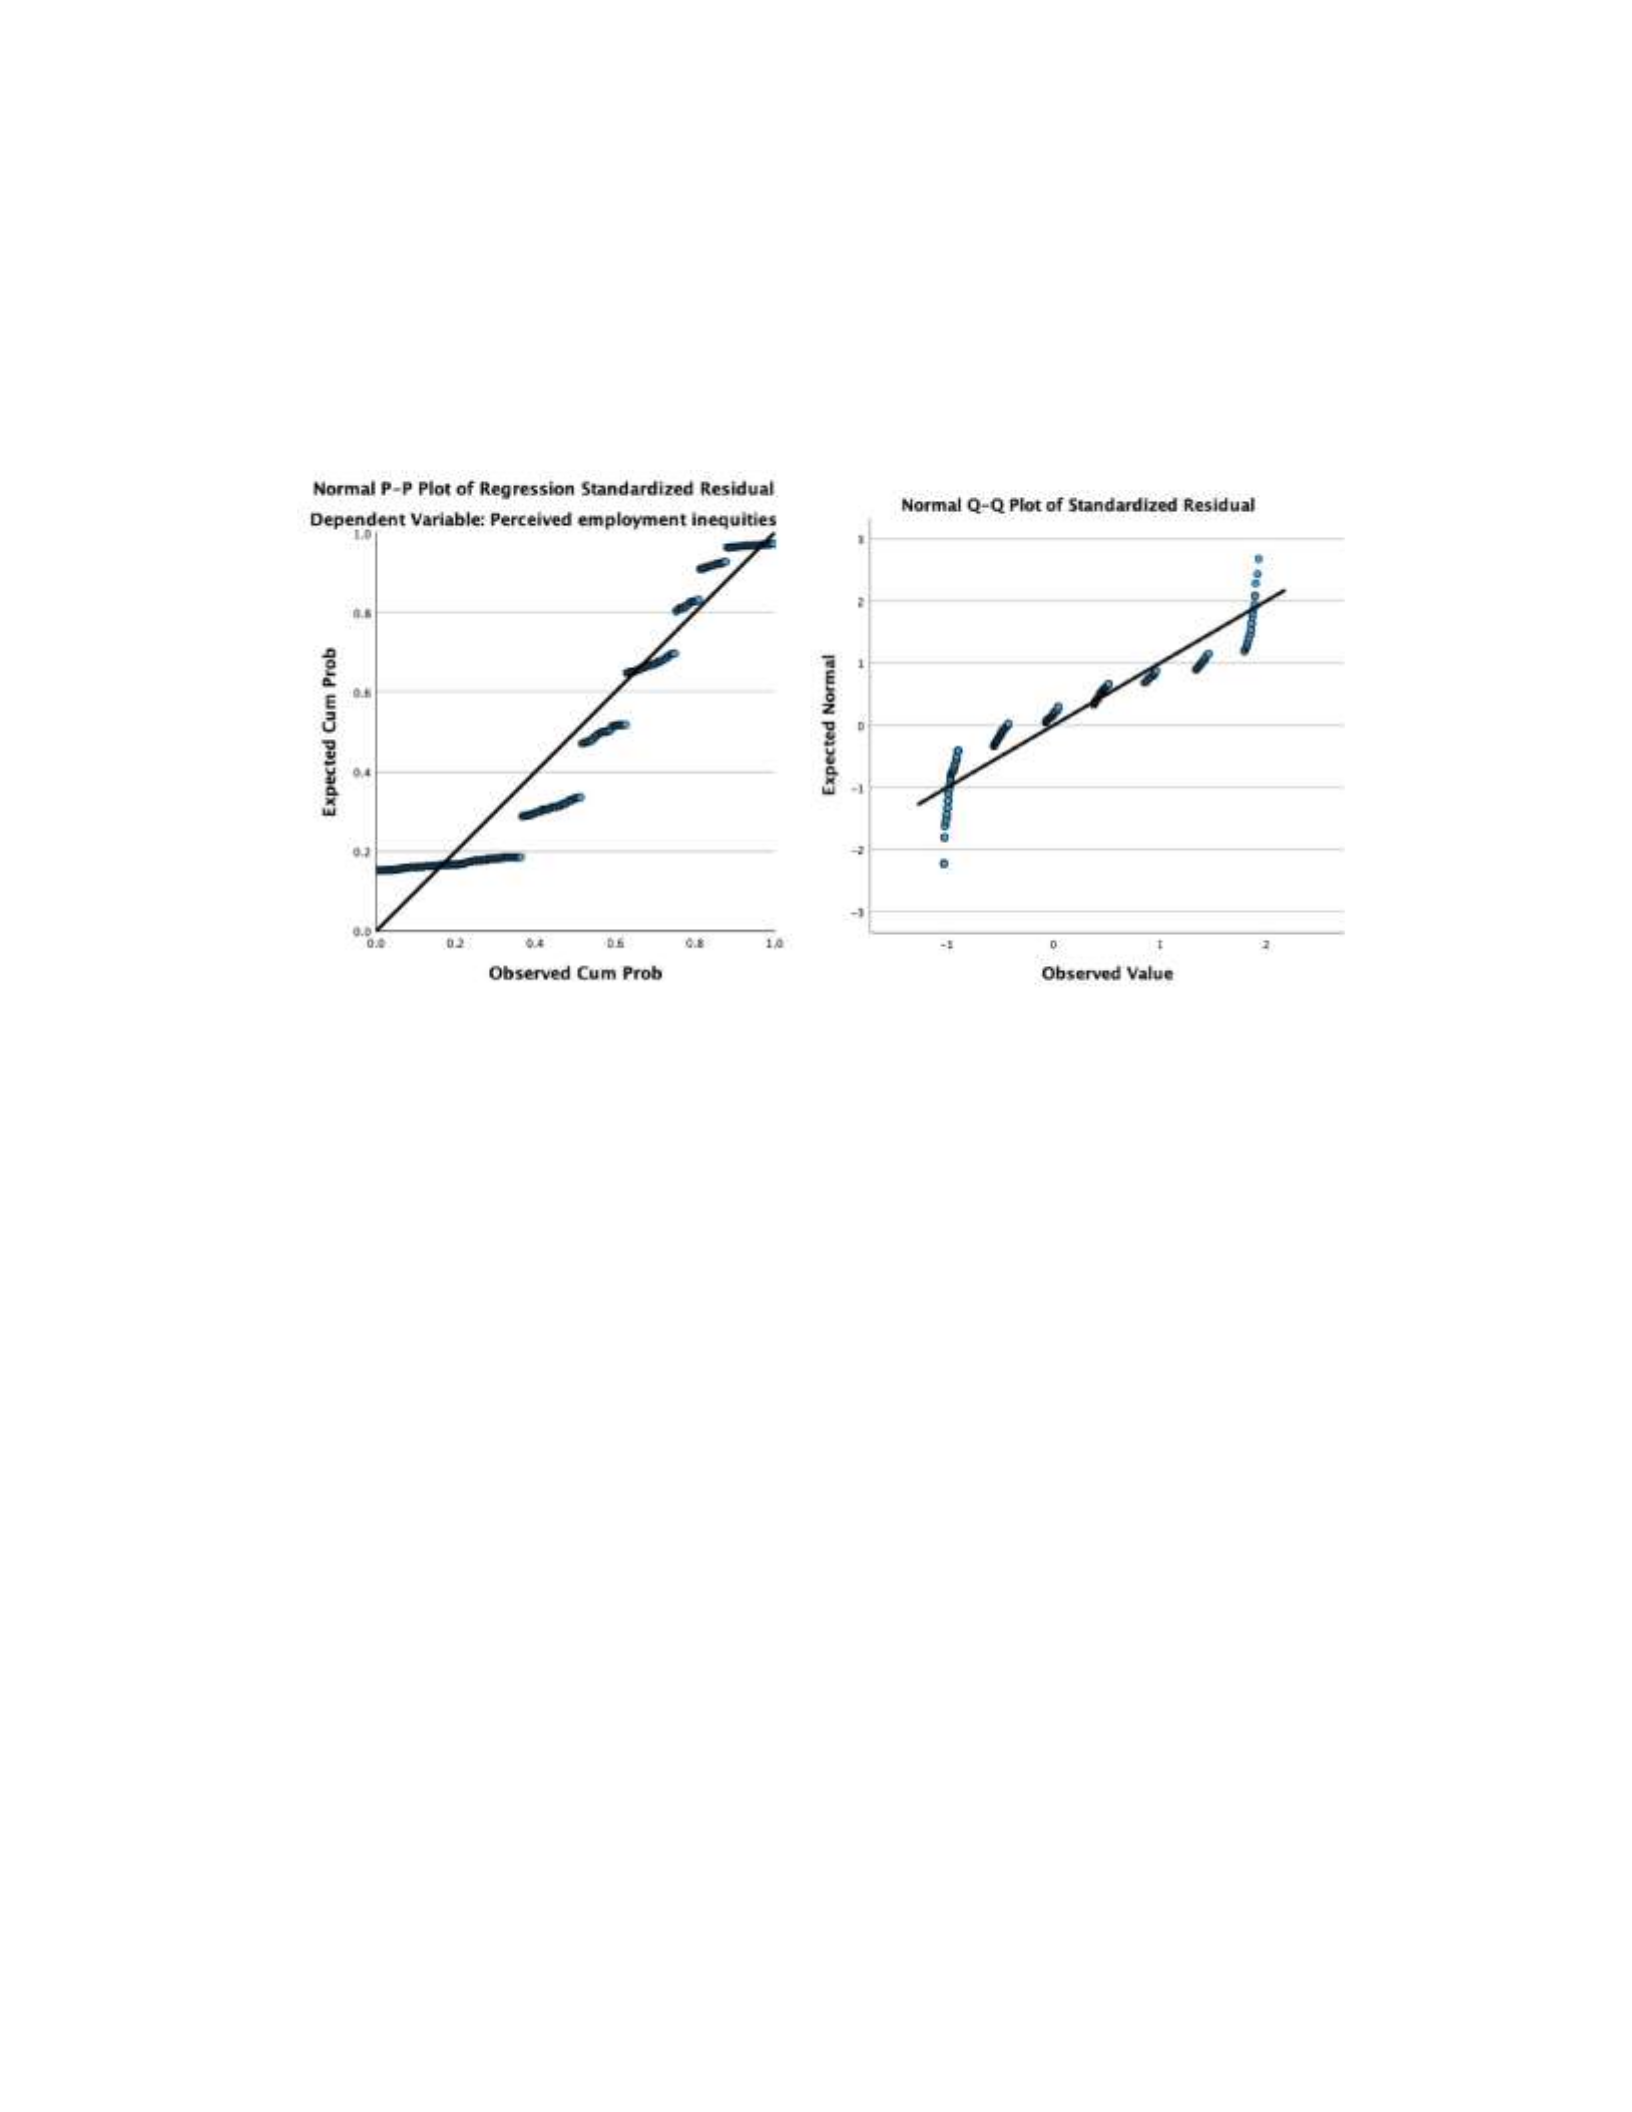
73
Figure 9
Normal P-P and Q-Q Plots of Residuals—Perceived Employment Inequities
To approach RQ2 (What is the relationship between non-affirmation of gender
identity and perceived employment inequities?), a simple linear regression analysis was
conducted to evaluate the prediction of perceived employment inequities (Table 5) from
non-affirmation of gender identity. The results of the linear regression analysis (Tables
10-12) reveal that non-affirmation of gender identity not to be a statistically significant
predictor of the model (p = .50), as shown in Table 12. The regression coefficient [B =
.012, 95% C.I. (-.022, .046), p = .495] associated with non-affirmation of gender identity
suggests that with each additional point on the 24-point composite scale (Table 2)
indicating non-affirmation of gender identity, I cannot say whether perceived employment
inequities will increase or decrease.
The R2 value of [0.042] (Table 12) associated with this regression model suggests
that non-affirmation of gender identity accounts for only 4.2% of the variation in
74
healthcare stereotype threat, which means that 95.8% of the variation cannot be explained
by non-affirmation of gender identity alone. The confidence interval of (-.022, .046) for
non-affirmation of gender identity associated with the regression analysis contains 0,
which means the null hypothesis, there is no association between the degree of
nonaffirmation of gender identity and perceived employment inequities, cannot be
rejected.
Table 10
Model Summary for Nonaffirmation of Gender Identity and Perceived Employment
Inequities
Model Summarya
Model
R
R Square
Adjusted R
Square
Std. Error of
the Estimate
1
.042a
.002
-.002
2.12867
a. Predictors: (Constant); Non-affirmation of gender identity
b. Dependent Variable: Perceived employment inequities
Table 11 shows the model proposed predicting negative employment outcomes as
a function of non-affirmation of gender identity does not perform statistically
significantly better than the null model, which simply estimates negative employment
outcomes as the sample mean (F = .467, p-value =. 495).
Table 11
ANOVA Nonaffirmation of Gender Identity and Perceived Employment Inequities
ANOVAa
Model Sum of df Mean F Sig.
Squares Square
1 Regression 2.114 1 2.114 .467 .495b

75
Residual 1196.251 264 4.531
Total 1198.365 265
a. Dependent Variable: Perceived employment inequities
b. Predictors: (Constant); Non-affirmation of gender identity
Table 12 shows the average index for perceived employment inequities is 1.91.
Non-affirmation of gender identity does not have a statistically significant impact in this
sample. Although the coefficient for non-affirmation of gender identity suggests that for
each additional point of increase in the non-affirmation of gender identity experienced by
trans participants in the survey, perceived employment inequities increase by 0.012 points
(t = .683, p-value = .495). However, because the p-value is quite large, it cannot be
determined whether non-affirmation of gender identity has a positive, negative, or no
impact on perceived employment inequities.
Table 12
Coefficients for Nonaffirmation of Gender Identity and Perceived Employment Inequities
Coefficientsa
Unstandardized
B
Coefficients
Std. Error
Standardized
Coefficients
Beta
t
Sig.
(Constant)
1.905
.248
7.694
<.011
Non-affirmation of
Gender Identity
.012
.017
.042
.683
.495
a. Dependent Variable: Perceived employment inequities
There were two emerging hypotheses from the data analysis. The results show that
more research is needed surrounding the TGD community when looking specifically at
perceived employment inequities. The question is not, “Is there discrimination,” but

76
rather, “What level of discrimination does the TGD community face versus their
cisgender coworkers?”
Summary
The purpose of this quantitative retrospective quasi-experimental study was to
examine whether there is a relationship between the non-affirmation of gender identity,
healthcare stereotype threat, and perceived employment inequities concerning employees
in healthcare systems and organizations. The exploratory data analysis was performed to
present the characteristics of the data sets.
The results of RQ1 (What is the relationship between non-affirmation of gender
identity and healthcare stereotype threat?) showed that non-affirmation of gender identity
is a statistically significant predictor of healthcare stereotype threat. The null hypothesis
(there is no relationship between non-affirmation of gender identity and healthcare
stereotype threat) was rejected. The alternative hypothesis (a relationship exists between
non-affirmation of gender identity and healthcare stereotype threat) was accepted. RQ2
(What is the relationship between non-affirmation of gender identity and perceived
employment inequities?) showed that non-affirmation of gender identity is not a
statistically significant predictor of perceived employment inequities. The null hypothesis
(there is no statistically significant relationship between non-affirmation of gender
identity and perceived employment inequities) was retained. The alternative hypothesis
(there is a statistically significant relationship between non-affirmation of gender identity
and perceived employment inequities) was rejected. Section 4 discusses the conclusions
of the study and the possible reasons for the outcomes described in this section.

77
Limitations of the research and the shortcomings that were encountered during the
investigation will also be described. The section then provides a discussion on the
recommendations for future research, theory, and practice. The final section is then
concluded with a summary of the completed study.

78
Section 4: Application to Professional Practice and Implications for Social Change
Introduction
The purpose of this quantitative retrospective quasi-experimental study was to
examine whether there is a relationship between the non-affirmation of gender identity,
healthcare stereotype threat, and perceived employment inequities concerning employees
in healthcare systems and organizations. The nature of this study was to address the
research questions to investigate the correlation between non-affirmation of gender
identity, healthcare stereotype threat, and employment using secondary data from the
TransPop survey. This study is significant in that it fills in the gaps in the current
literature to extend knowledge of awareness and provide more support to the TGD
community in healthcare organizations, creating positive social change.
Through the secondary data analysis that was conducted, RQ1 (What is the
relationship between non-affirmation of gender identity and healthcare stereotype threat?)
showed that non-affirmation of gender identity is a statistically significant predictor of
healthcare stereotype threat. RQ2 (What is the relationship between non-affirmation of
gender identity and perceived employment inequities?) showed that non-affirmation of
gender identity is not a statistically significant predictor of perceived employment
inequities.
Interpretation of the Findings
The data analysis findings expanded the literature review in Section 1. The major
themes found throughout the exhaustive literature review were as follows: TGD
discrimination in healthcare environments, gender identity affirmation, bias in healthcare,

79
cultural norms surrounding cisgenderism, and the need for more education. The current
literature identified in the literature review in Section 1 provided an overview of barriers
to TGD patients in healthcare organizations; however, there was little to no literature on
personal awareness focusing on non-affirmation of a patient and employees’ gender
identity and ways to prevent harm to TGD patients and employees in healthcare. The
results of this study expand the findings from prior studies in which it examined the
impact of affirmation of the gender identity of patients and employees in healthcare
organizations. The specific aspects have not been addressed in prior research. The focus
on healthcare organizations, through the TransPop data set, concerning TGD patients and
employees was due to the lack of research done. The conducted analysis adds to the
literature by identifying the relationship between the independent and dependent variables
in RQ1.
In terms of the theoretical framework, the study’s findings align with the Sexual
citizenship theory by rights of civil society, such as a person's right to work and seek
healthcare for those who identify as TGD. Through this model, healthcare organizations
can evaluate their current structure and processes, such as how TGD patients and
employees access affirming care and have an affirming workplace. Sexual citizenship
theory is applicable and can be used to make sense of the literature review and data
analysis. However, there is no statistical significance between the non-affirmation of
gender identity and perceived employment inequities, as shown in Figure 9.
The scope of the study allowed for analysis and interpretation of the data provided
in the secondary quantitative dataset. The findings showed no statistically significant

80
relationship between non-affirmation of gender identity and perceived employment
inequities; however, there was a statistically significant relationship between
nonaffirmation of gender identity and healthcare stereotype threat.
Limitations of the Study
The limitations of this study included data, analysis, and the variable chosen such
as non-affirmation of gender identity versus gender identity. The TransPop survey was
conducted from 2016-2018, in the United States, through Gallop. Disclosure and privacy
safety are always a concern in the TGD community. Additionally, many of the data
collection surveys rely on self-reported data from the TGD individual and therefore may
not always be accurate as there is a possibility for bias by the TGD individual due to prior
trauma and past discrimination. RQ2 examined the non-affirmation of gender identity and
perceived employment inequities but using this independent variable the results focused
strictly on TGD individuals. The use of gender identity as the independent variable in
RQ2 would have examined the relationship between cisgender and TGD employees
regarding perceived employment inequities with possible statistical significance.
The results of this study may not be representative of all TGD individuals across
the United States. The determinants of health may vary from state to state depending on
anti-transgender laws and acceptance. The potential for generalizability was considered
but well understood that TGD participants are not all treated equally or receive
acknowledgment for their gender identity across healthcare organizations, whether the
organization is culturally competent and affirming. This is due to conducting an initial
assessment to identify the participant’s safety in disclosing and sharing experiences as

81
both a patient and an employee. Data about cisgender individuals were not used in this
study even though they were a part of the original survey. The data relationship of the
TGD and cisgender community with perceived employment inequities could have
expanded understanding of the inequities faced by the TGD community.
Recommendations
In this study, non-affirmation of gender identity, healthcare stereotype threat, and
perceived employment inequities were examined from the TransPop data set.
Recommendations for further research include quality of care for the TGD community
when their identity is not affirmed, analysis of transwomen and transfeminine individuals
around affirmation in healthcare treatment and employment inequities, and ways
healthcare administration tackles healthcare stereotype threats concerning the TGD
community. There is a lack of research surrounding euphoria in the TGD community
when seeking care or employment in healthcare in affirming environments.
This study was hindered by secondary data analysis and constraints of questions
asked to the participants. Research can examine how LGTBQI+ organizations and their
administrators best serve the TGD using their best practices to springboard better
longterm solutions to health disparities, bias, and discrimination. Research using holistic
solutions to provide care and social support for the TGD community.
Additional research is needed that focuses on how healthcare organizations tackle
bias around the TGD community in the long term. There are plenty of examples of how
healthcare organizations are harming the TGD community but fewer that are creating safe
and affirming environments for the TGD community. Further research can examine ways

82
that affirming space has improved the health and well-being of the TGD community
through ongoing cultural competency training, policy changes, affirmation by senior
leadership staff, and acceptance of gender identity.
Implications for Professional Practice and Social Change
Due to the ongoing anti-transgender legislation that is sweeping across the United
States, healthcare professionals struggle to best serve their TGD patients. Some
healthcare organizations are faith-based (Khaikin & Uttley, 2016) adding challenges of
religious beliefs to overshadow the care needs of the TGD community. Based on the
review of literature as mentioned in section one and the literature review, theoretical
framework, and analysis developed by this research, the study recommends several
changes to professional practice. The following suggestions are aimed at improving the
overall healthcare environment for TGD patients and employees in the United States.
First, it is recommended that healthcare administrators and healthcare leaders
review policy around cultural competency, how biases are addressed, and how safe and
affirming the organization is. Education for all healthcare staff is a resounding theme in
the literature. Instruction recommendations are ongoing training on understanding bias
and intersectionality of identities, how to affirm the gender identity of all staff cisgender
and transgender, and trauma-informed care and support (Boot-Haury, 2023). While these
training courses are not intended to be a fix, they can serve as a foundation for social
change and provide safer spaces with empathy and compassion for all who receive care
and come to work. The training requires that all staff working in healthcare environments
receive training that helps them create social and cultural change in the organization.

83
In addition to these recommended changes, promoting spaces where patients and
employees can be their authentic selves and not have to conform to binary rules supports
the TGD community. This requires patients and their families, staff, and volunteers to
enter the healthcare environment as themselves. This authenticity requires medical
records to reflect their gender identity and sexual orientation. Additionally, it opens space
to treat the whole patient including their family, homelessness, and lifestyle, not just
symptoms. Understanding and support of the patient and staff is more than just their level
of status in the organization. It will require every staff member from the CEO down to
entry-level staff members to ensure they are asking for and honoring the identities of
patients and staff through advocacy for every person.
Finally, healthcare organizations could lead the charge of ensuring equity by
speaking up against laws based on misconceptions and myths surrounding the TGD
community. Connecting with state and local legislators as a proponent for laws that
support and ensure the TGD community. Additionally, being a vocal advocate of the TGD
community that they serve can be achieved by scoring high on the Health Equity Index
through organizations like the Human Rights Campaign.
Future recommendations for research could include looking at the relationship
between gender identity and perceived employment inequities. This study showed that
there is a statistically significant relationship between the non-affirmation of gender
identity and healthcare stereotype threat showing a correlation of discrimination in
healthcare. The difference between being cisgender and transgender can lead to whether a
person is hired or fired at their workplace requiring employers to take action to stop harm

84
in their workplace. Another recommendation for research could include gender identity,
age, and perceived employment inequities. As the TGD community continues to age, how
will that affect their job status and discrimination?
Conclusions
The review of literature, theoretical framework, and analysis from this study
establishes the relationship between non-affirmation of gender identity and healthcare
stereotype threat. The purpose of this quantitative retrospective quasi-experimental study
was to examine whether there is a relationship between the non-affirmation of gender
identity, healthcare stereotype threat, and perceived employment inequities that TGD
employees face in healthcare systems and organizations. The questions that were used to
address the research problem identified in the purpose of the study were as follows: RQ1:
What is the relationship between non-affirmation of gender identity and healthcare
stereotype threat?
RQ2: What is the relationship between non-affirmation of gender identity and
perceived employment inequities?
The reason the study was conducted, the key findings, interpretations, limitations
of the study, recommendations for future research, applications to professional practice,
and implications for social change have been reviewed.
Through the literature review, discrimination and bias around gender identity
require additional consideration with ways of addressing and improving the needs of the
TGD community in healthcare. The bias and harm from not being affirmed spill over into
the employment status of the TGD individuals working in healthcare organizations.

85
Through the secondary data analysis that was conducted, RQ1 (What is the
relationship between non-affirmation of gender identity and healthcare stereotype threat?)
showed that non-affirmation of gender identity is a statistically significant predictor of
healthcare stereotype threat. RQ2 (What is the relationship between non-affirmation of
gender identity and perceived employment inequities?) showed that non-affirmation of
gender identity is not a statistically significant predictor of perceived employment
inequities. Through the theoretical framework, this study’s findings align with the sexual
citizenship theory by rights of civil society in which a person's right is to work and seek
healthcare for those who identify as TGD. With this model, healthcare organizations must
examine the rights of their patients and employees ensuring that they are affirming to
everyone who enters their doors.
This study’s findings have impacts on positive social change as it relates to the
TGD and healthcare organizations. This study is significant in that it can help to identify
ways healthcare administrators can ensure the safety of their patients and employees
within the organization and reflect those they serve. Recommendations for further
research include how healthcare organizations tackle bias around the TGD community
long-term. Further research can examine ways that affirming space has improved the
health and well-being of the TGD community and the acceptance of gender identity for
all people.
References
Abdou, C. M., Fingerhut, A. W., Jackson, J. S., & Wheaton, F. (2016). Healthcare
stereotype threat in older adults in the health and retirement study. American

86
Journal of Preventive Medicine, 50(2), 191–198.
https://doi.org/10.1016/j.amepre.2015.07.034
Adegoke, A.O. (2018). On the Effects of Nonlinearity Between Variables on the
Correlation Coefficient. [University of Regina].
Arayasirikul, S., & Wilson, E. C. (2019). Spilling the t on trans-misogyny and
microaggressions: An intersectional oppression and social process among trans
women. Journal of Homosexuality, 66(10), 1415–1438.
https://doi.org/10.1080/00918369.2018.1542203
Asamoah, M. K. (2014). Re-examination of the limitations associated with correlational
research. Journal of Educational Research and Reviews, 2(4), 45–52.
Baboolall, D., Greenberg, S., Obeid, M., & Zucker, J. (2022). Being transgender at work.
McKinsey Quarterly, 1, 1–18.
Blackwell, C. W., Diaz-Cruz, A., & Yan, X. (2020). Equality and quality: The relationship
between Magnet® status and healthcare organizational commitment to lesbian,
gay, bisexual, and transgender equality. Journal of Social Service
Research, 46(5), 705–712. https://doi.org/10.1080/01488376.2019.1645796
Blazucki, S. (2023). The Equal Rights Amendment and the Equality Act: Closing Gaps
Post-Bostock for Sexual Orientation and Gender Identity Minorities. University of
the District of Columbia Law Review, 26 (1), Article 4.
Boe, J. L., Ellis, E. M., Sharstrom, K. A., & Gale, J. E. (2020). Disrupting cisnormativity,
transnormativity, and transmisogyny in healthcare: Advancing trans inclusive
practices for medical family therapists. Journal of Feminist Family Therapy,
32(3/4), 157–175. https://doi.org/10.1080/08952833.2020.1848051

87
Boot-Haury, J. W. (2023). A preliminary study of intensive transgender-specific cultural
competency training: Implications for social workers and psychologists who work
with rural transgender clients. Journal of Gay & Lesbian Social Services, 1–27.
https://doi.org/10.1080/10538720.2023.2266399
Brothers, K., Rivera, S., Cadigan, R., Sharp, R., & Goldenberg, A. (2019). A Belmont
reboot: Building a normative foundation for human research in the 21st century.
Journal of Law, Medicine & Ethics, 47(1), 165-172.
https://doi.org/10.1177/1073110519840497
Burgess, D. J., Warren, J., Phelan, S., Dovidio, J., & van Ryn, M. (2010). Stereotype
threat and health disparities: What medical educators and future physicians need
to know. Journal of General Internal Medicine, 25 Suppl 2(Suppl 2), S169–S177.
https://doi.org/10.1007/s11606-009-1221-4
Cabacungan, A., Lee, J., Chaney, B., & Averett, P. (2019). Does gender minority
professional experience impact employment discrimination? Two résumé
experiments. Journal of Youth Development, 14(4), 267–284.
https://doi.org/10.5195/jyd.2019.829
Canvin, L., Twist, J., & Solomons, W. (2023). “I don’t want to say the wrong thing”:
Mental health professionals’ narratives of feeling inadequately skilled when
working with gender diverse adults. Psychology & Sexuality, 14(2), 337–350.
https://doi.org/10.1080/19419899.2022.2118070
Castañeda, E., & Smith, C. (2023). Conducting research with marginalized populations:
Methodological, ethical, and IRB considerations. Journal of Applied Social
Sciences (19367244), 17(1), 111–131.

88
https://doi.org/10.1177/19367244221141326
Casey, L. S., Reisner, S. L., Findling, M. G., Blendon, R. J., Benson, J. M., Sayde, J. M.,
& Miller, C. (2019). Discrimination in the United States: Experiences of lesbian,
gay, bisexual, transgender, and queer Americans. Health Services Research, 54,
1454–1466. https://doi.org/10.1111/1475-6773.13229
Chirkov, V., & Anderson, J. (2018). Statistical positivism versus critical scientific realism
A comparison of two paradigms for motivation research: Part 1 A philosophical
and empirical analysis of statistical positivism. Theory &
Psychology, 28(6), 712–736. https://doi.org/10.1177/0959354318804670
Creswell, J. W., & Creswell, J. D. (2018). Research design: Qualitative, quantitative, and
mixed methods approaches. (5th ed.). SAGE Publications, Inc.
Dahlen, S. (2020). De-sexing the medical record? An examination of sex versus gender
identity in the general medical council’s trans healthcare ethical advice. New
bioethics, 26(1), 38–52. https://doi.org/10.1080/20502877.2020.1720429
Davidson, S., & Halsall, J. (2016). Gender inequality: Nonbinary transgender people in
the workplace. Cogent Social Sciences, 2(1), N.PAG.
https://doi.org/10.1080/23311886.2016.1236511
Davidson, S. (2016, August 16). Gender inequality: Nonbinary transgender people in the
workplace. Cogent Social Sciences, Volume 2, Issue 1.
https://www.tandfonline.com/doi/full/10.1080/23311886.2016.1236511
DiPalma, L. M. (2021). Gender and sexual orientation in the workplace. Research
Starters: Sociology.

89
Dixon, J., & Dougherty, D. S. (2014). A language convergence/meaning divergence
analysis exploring how LGBTQ and single employees manage traditional family
expectations in the workplace. Journal of Applied Communication
Research, 42(1), 1–19. https://doi.org/10.1080/00909882.2013.847275
Doyle, D. M. (2022). Transgender identity: development, management and affirmation.
Current Opinion in Psychology, 48.
https://doi.org/10.1016/j.copsyc.2022.101467
Doyle, D. M., Begeny, C. T., Barreto, M., & Morton, T. A. (2021). Identity-related factors
protect well-being against stigma for transgender and gender nonconforming
people. Archives of Sexual Behavior, 50(7), 3191–3200.
https://doi.org/10.1007/s10508-021-02029-1
Elias, N. M. R. (2017). Constructing and implementing transgender policy for public
administration. Administration & Society, 49(1), 20–47.
https://doi.org/10.1177/0095399716684888
Enders, F. T., Golembiewski, E. H., Pacheco-Spann, L. M., Allyse, M., Mielke, M. M., &
Balls-Berry, J. E. (2021). Building a framework for inclusion in health services
research: Development of and pre-implementation faculty and staff attitudes
toward the Diversity, Equity, and Inclusion (DEI) plan at Mayo Clinic. Journal of
Clinical & Translational Science, 5(1), 1–10. https://doi.org/10.1017/cts.2020.575
Flynn, M. K., & Bhambhani, Y. (2021). Internalized transphobia, nondisclosure of gender
identity, and life satisfaction among transgender and non-binary adults:
The moderating roles of psychological flexibility and inflexibility. Journal of

90
Contextual Behavioral Science, 20, 194–201.
https://doi.org/10.1016/j.jcbs.2021.04.008
Frankfort-Nachmias, C., Leon-Guerrero, A., Davis, G. (2021). Social statistics for a
diverse society (9th ed.). SAGE Publications, Inc.
Freedman, D. A. (2005). Statistical Models: Theory and Practice. Cambridge University
Press.
Friesen, P., Kearns, L., Redman, B., & Caplan, A. L. (2017). Rethinking the Belmont
Report? American Journal of Bioethics, 17(7), 15–21.
https://doi.org/10.1080/15265161.2017.1329482
Galupo, M. P., & Resnick, C. A. (2016). Experiences of LGBT microaggressions in the
workplace: Implications for policy. In T. Köllen (Ed.), Sexual orientation and
transgender issues in organizations (pp. 271-287).
Springer. https://doi.org/10.1007/978-3-319-29623-4_16
Ghosh, B. (2022). State, citizenship and gender-variant communities in India. Citizenship
Studies, 26(2), 127–145. https://doi.org/10.1080/13621025.2021.2024147
Giffort, D. M., & Underman, K. (2016). The relationship between medical education and
trans health disparities: a call to research. Sociology Compass, 10(11), 999–1013.
https://doi.org/10.1111/soc4.12432
Goldbach, C., Knutson, D., & Kler, S. (2021). The SAGE Encyclopedia of Trans Studies
(Vols. 1–2). SAGE Publications, Inc. https://doi.org/10.4135/9781544393858
Goldenberg, T., Reisner, S. L., Harper, G. W., Gamarel, K. E., & Stephenson, R. (2020).
State policies and healthcare use among transgender people in the U.S. American

91
Journal of Preventive Medicine, 59(2), 247–259.
https://doi.org/10.1016/j.amepre.2020.01.030
Goszkowicz, K., & Davis, P. (2023). Reducing Adult transgender barriers to care in the
emergency department: strategies to improve policies and practices. Advanced
Emergency Nursing Journal, 45(1), 3–10.
https://doi.org/10.1097/TME.0000000000000446
Green, E. & Mauer, L. (2015). Glossary of transgender terms, The Teaching Transgender
Toolkit. Second Edition, 53-56.
Hasan, M. N. (2016). Positivism: to what extent does it aid our understanding of the
contemporary social world? Quality & Quantity, 50(1), 317–325.
https://doi.org/10.1007/s11135-014-0150-4
Hazra, A., & Gogtay, N. (2016). Biostatistics Series Module 6: Correlation and Linear
Regression. Indian Journal of Dermatology, 61(6), 593–601.
https://doi.org/10.4103/0019-5154.193662
Herman, J., Flores, A., & O’Neill, K. (2022, June). How many adults and youth identify
as transgender in the United States? UCLA School of Law Williams Institute.
https://williamsinstitute.law.ucla.edu/wp-content/uploads/Trans-Pop-Update-
Jun2022.pdf
Hossain, M., Atif, M., Ahmed, A., & Mia, L. (2020). Do LGBT workplace diversity
policies create value for firms? Journal of Business Ethics, 167(4), 775–791.
https://doi.org/10.1007/s10551-019-04158-z

92
Huffman, A. H., Mills, M. J., Howes, S. S., & Albritton, M. D. (2021). Workplace support
and affirming behaviors: moving toward a transgender, gender diverse, and non-
binary friendly workplace. International Journal of Transgender
Health, 22(3), 225–242. https://doi.org/10.1080/26895269.2020.1861575
Hughto, J. M. W., Gunn, H. A., Rood, B. A., & Pantalone, D. W. (2020). Social and
medical gender affirmation experiences are inversely associated with mental
health problems in a U.S. non-probability sample of transgender adults. archives
of sexual behavior, 49(7), 2635–2647. https://doi.org/10.1007/s10508-020-01655-
5
Human Rights Campaign Foundation. (2022). Health equality index: promoting equitable
and inclusive care for LGBTQ+ patients and their families. Washington, DC.
Johnson, A. H., Hillb, I., Beach-Ferrara, J., Rogers, B. A., & Bradford, A. (2020).
Common barriers to healthcare for transgender people in the U.S.
Southeast. International Journal of Transgender Health, 21(1), 70–78.
https://doi.org/10.1080/15532739.2019.1700203
Kanamori, Y., & Cornelius-White, J. H. D. (2016). Big changes, but are they big enough?
Healthcare professionals’ attitudes toward transgender persons. International
Journal of Transgenderism, 17(3/4), 165–175.
https://doi.org/10.1080/15532739.2016.1232628
Kattari, S. K., Bakko, M., Hecht, H. K., & Kattari, L. (2020). Correlations between
healthcare provider interactions and mental health among transgender and
nonbinary adults. SSM: Population Health, 10.

93
https://doi.org/10.1016/j.ssmph.2019.100525
Katz-Wise, S. L., Boskey, E. R., Godwin, E. G., Thomson, K., Post, J., & Gordon, A. R.
(2022). “We’re moving in the right direction. Still a long way to go”: Experiences
and perceptions of the climate for LGBTQ+ employees at a pediatric hospital.
Journal of Homosexuality, 69(13), 2286–2304.
https://doi.org/10.1080/00918369.2021.1938468
Khaikin, C. & Uttley, L. (2016) Growth of catholic hospitals and health systems: 2016
update of the miscarriage of medicine report. Merger Watch.
http://static1.1.sqspcdn.com/static/f/816571/27061007/1465224862580/MW_Upd
ate-2016-
MiscarrOfMedicinereport.pdf?token=rf3rsQaaCVCzLV9hKOIHuFcaWiU%3D.
King, W. M., & Gamarel, K. E. (2021). A scoping review examining social and legal
gender affirmation and health among transgender populations. Transgender
Health, 6(1), 5–22. https://doi.org/10.1089/trgh.2020.0025
Kleintop, L. K. (2019). When transgender employees come out: perceived support and
cultural change in the transition process. Journal of Business Diversity, 19(5), 55–
67. https://doi.org/10.33423/jbd.v19i5.2645
Koch, J. M., McLachlan, C., Victor, C. J., Westcott, J., & Yager, C. (2020). The cost of
being transgender: where socio-economic status, global health care systems, and gender
identity intersect. Psychology & Sexuality, 11(1–2), 103–119.
https://doi.org/10.1080/19419899.2019.1660705

94
Krueger, E. A., Divsalar, S., Luhur, W., Choi, S. K., & Meyer, I. H. (2020). TransPop -
U.S. Transgender Population Health Survey (Methodology and Technical Notes).
Los Angeles, CA: The Williams Institute. Retrieved from:
https://www.transpop.org/s/TransPop-Survey-Methods-v18-FINAL-copy.pdf
Lakens, D., & Caldwell, A. R. (2021). Simulation-based power analysis for factorial
analysis of variance designs. Advances in Methods and Practices in Psychological
Science. https://doi.org/10.1177/2515245920951503
Leppel, K. (2016). The labor force status of transgender men and women. International
Journal of Transgenderism, 17(3/4), 155–164.
https://doi.org/10.1080/15532739.2016.1236312
Leppel, K. (2021). Transgender men and women in 2015: employed, unemployed, or not
in the labor force. Journal of Homosexuality, 68(2), 203–229.
https://doi.org/10.1080/00918369.2019.1648081
Lerner, J. E., Martin, J. I., & Gorsky, G. S. (2021). More than an apple a day: factors
associated with avoidance of doctor visits among transgender, gender
nonconforming, and nonbinary people in the USA. Sexuality Research & Social
Policy: Journal of NSRC, 18(2), 409–426. https://doi.org/10.1007/s13178-020-
00469-3
Liu, M., Sandhu, Keuroghlian, A, (2022, July 28). Achieving the triple aim for sexual and
gender minorities. The New England Journal of Medicine, 2022; 387:294-297. http://doi/
10.1056/NEJMp2204569

95
McGregor, B., Belton, A., Henry, T. L., Wrenn, G., & Holden, K. B. (2019). Improving
behavioral health equity through cultural competence training of health care
providers. Ethnicity & Disease, 29, 359–364.
https://doi.org/10.18865/ed.29.S2.359
McNulty, Y., McPhail, R., Inversi, C., Dundon, T., & Nechanska, E. (2018). Employee
voice mechanisms for lesbian, gay, bisexual and transgender expatriation: the role
of Employee-Resource Groups (ERGs) and allies. International Journal of
Human Resource Management, 29(5), 829–856.
https://doi.org/10.1080/09585192.2017.1376221
Meyer, H. (2016). Dignity’s transgender bias case could signal more religious freedom
clashes. Modern Healthcare, 46(33), 10–11.
Meyer, I. (2021) TransPop, United States, 2016-2018. Interuniversity Consortium for
Political and Social Research. https://doi.org/10.3886/ICPSR37938.v1
Meyer, I. H., Wilson, B. D. M., & O'Neill, K. (2021). LGBTQ people in the US: Select
findings from the generations and TransPop studies. Williams Institute, UCLA
School of Law.
Mizock, L., Woodrum, T. D., Riley, J., Sotilleo, E. A., Yuen, N., & Ormerod, A.
J. (2017). Coping with transphobia in employment: strategies used by transgender
and gender-diverse people in the United States. International Journal of
Transgenderism, 18(3), 282–294.
https://doi.org/10.1080/15532739.2017.1304313

96
Nadal, K. L., Whitman, C. N., Davis, L. S., Erazo, T., & Davidoff, K. C. (2016).
Microaggressions toward lesbian, gay, bisexual, transgender, queer, and
genderqueer people: a review of the literature. Journal of Sex Research, 53(4/5),
488–508. https://doi.org/10.1080/00224499.2016.1142495
Newman, C. E., Prankumar, S. K., Cover, R., Rasmussen, M. L., Marshall, D., &
Aggleton, P. (2021). Inclusive health care for LGBTQ+ youth: support, belonging,
and inclusivity labour. Critical Public Health, 31(4), 441–450.
https://doi.org/10.1080/09581596.2020.1725443
Owens, B., Mills, S., Lewis, N., & Guta, A. (2022). Work-related stressors and mental
health among LGBTQ workers: Results from a cross-sectional survey. PLoS
ONE, 17(10), 1–14. https://doi.org/10.1371/journal.pone.0275771
Parr, N. J., & Howe, B. G. (2020). Factors associated with frequency of gender identity
non-affirmation microaggressions among transgender persons. Culture, Health &
Sexuality. https://doi.org/10.1080/13691058.2020.1755454
Perales, F., Ablaza, C., Tomaszewski, W., & Emsen-Hough, D. (2021). You, me, and
them: understanding employees’ use of trans-affirming language within the
workplace. Sexuality Research & Social Policy: A Journal of the NSRC.
https://doi.org/10.1007/s13178-021-00592-9
Perone, A. K. (2020). Protecting health care for transgender older adults amidst a
backlash of US federal policies. Journal of Gerontological Social Work, 63(8),
743–752. https://doi.org/10.1080/01634372.2020.1808139
Petchko, K. (2018). How to write about economics and public policy. Academic Press,
271-300. https://doi.org/10.1016/B978-0-12-813010-0.00014-4.

97
Piegza, M., & Główczyński, P. (2022). Minority stress and selected mental disorders in
people with gender dysphoria and gender incongruence – a narrative review.
Medycyna Pracy, 73(2), 163–172.
https://doi.org/10.13075/mp.5893.01198
Reisner, S. L., Gamarel, K. E., Mizock, L., White Hughto, J. M., Keuroghlian, A. S., &
Pachankis, J. E. (2016). Discriminatory experiences associated with posttraumatic
stress disorder symptoms among transgender adults. Journal of Counseling
Psychology, 63(5), 509–519. https://doi.org/10.1037/cou0000143
Reisner, S. L., & Hughto, J. M. W. (2019). Comparing the health of non-binary and
binary transgender adults in a statewide non-probability sample. PLoS
ONE, 14(8), 1–20. https://doi.org/10.1371/journal.pone.0221583
Reisner, S. L., Hughto, J. M. W., Dunham, E. E., Heflin, K. J., Begenyi, J. B. G., Coffey,
E. J., & Cahill, S. (2015). Legal protections in public accommodations settings: a
critical public health issue for transgender and gender-nonconforming people.
Milbank Quarterly, 93(3), 484–515. https://doi.org/10.1111/1468-
0009.12127
Reisner, S. L., Moore, C. S., Asquith, A., Pardee, D. J., & Mayer, K. H. (2020). Gender
non-affirmation from cisgender male partners: development and validation of a
brief stigma scale for HIV research with transgender men who have sex with men
(Trans MSM). AIDS & Behavior, 24(1), 331–343. https://doi.org/10.1007/s10461-
019-02749-5
Robinson, M. (2020). Two-spirit identity in a time of gender fluidity. Journal of
Homosexuality, 67(12), 1675–1690.

98
https://doi.org/10.1080/00918369.2019.1613853
Rood, B. A., Puckett, J. A., Reisner, S. L., Maroney, M. R., Berman, A. K., & Pantalone,
D. W. (2017). Identity concealment in transgender adults: A qualitative assessment
of minority stress and gender affirmation. American Journal of
Orthopsychiatry, 87(6), 704–713. https://doi.org/10.1037/ort0000303
Rosich, Gina R. (2020). Sexual citizenship theory and employment discrimination among
transgender-identified people. Societies, 10(1), 17.
https://doi.org/10.3390/soc10010017
Rouse, M., Jr., & Hamilton, E. (2021). Rethinking sex and the brain: how to create an
inclusive discourse in neuroscience. Mind, Brain, and Education, 15(2), 163–167. Rusow,
J. A., Hidalgo, M. A., Calvetti, S., Quint, M., Wu, S., Bray, B. C., & Kipke, M.
D. (2022). Health and service utilization among a sample of gender-diverse youth
of color: the TRUTH study. BMC Public Health, 22(1), 1–13.
https://doi.org/10.1186/s12889-022-14585-9
Saunders, R. K., Carr, D. C., & Burdette, A. M. (2023). Health care stereotype threat and
sexual and gender minority well-being. journal of health & social behavior, 1.
https://doi.org/10.1177/00221465231205549
Sawyer, K., & Thoroughgood, C. (2017). Gender non-conformity and the modern
workplace: new frontiers in understanding and promoting gender identity
expression at work. Organizational Dynamics, 46(1), 1–8.
https://doi.org/10.1016/j.orgdyn.2017.01.001
Scott, D., Pereira, N. M., Harrison, S. E., Zarwell, M., Sanasi-Bhola, K., & Poteat, T.

99
(2021). “In the Bible Belt:” The role of religion in HIV care and prevention for
transgender people in the United States south. Health & Place, 70, N.PAG.
https://doi.org/10.1016/j.healthplace.2021.1
Seelman, K. L., & Poteat, T. (2020). Strategies used by transmasculine and non-binary
adults assigned female at birth to resist transgender stigma in healthcare.
International Journal of Transgender Health, 21(3), 350–365.
https://doi.org/10.1080/26895269.2020.1781017
Serano, J. (2021). The SAGE Encyclopedia of Trans Studies (Vols. 1-2). SAGE
Publications. https://dx.doi.org/10.4135/9781544393858
Sevelius J. (2013). Gender affirmation: a framework for conceptualizing risk behavior
among transgender women of color. Sex Roles. 68(11–12):675–689.
https://doi.org/10.1007/s11199-012-0216-5
Sherman, B., Kelly, R., & Payne-Foster, P. (2021). Integrating workforce health into
employer diversity, equity, and inclusion efforts. American Journal of Health
Promotion, 35(5), 609–612. https://doi.org/10.1177/0890117120983288
Siad, F. & Rabi, D. (2021). Harassment in the field of medicine: cultural barriers to
psychological safety. CJC Open, 3(12), S174–S179.
https://doi.org/10.1016/j.cjco.2021.08.018
Smart, B. D., Mann-Jackson, L., Alonzo, J., Tanner, A. E., Garcia, M., Refugio Aviles,
L., & Rhodes, S. D. (2022). Transgender women of color in the US South: A
qualitative study of social determinants of health and healthcare perspectives.
International Journal of Transgender Health, 23(1–2), 164–177.
https://doi.org/10.1080/26895269.2020.1848691

100
Stewart, C. (2020). The future is queer kids: Queering the homonormative temporalities
of same-sex marriage. Politics, 40(3), 265–280.
https://doi.org/10.1177/0263395719872595
Stroumsa, D., Shires, D. A., Richardson, C. R., Jaffee, K. D., & Woodford, M. R. (2019).
Transphobia rather than education predicts provider knowledge of transgender
health care. Medical Education, 53(4), 398–407.
https://doi.org/10.1111/medu.13796
Szemanski, A. (2020). When trans rights are disability rights: the promises and perils of
seeking gender dysphoria coverage under the Americans with disabilities act.
Harvard Journal of Law & Gender, 43(1), 137–168.
Taber, J. M., Howell, J. L., Emanuel, A. S., Klein, W. M. P., Ferrer, R. A., & Harris, P.
R. (2016). Associations of spontaneous self-affirmation with health care
experiences and health information seeking in a national survey of US adults.
Psychology & Health, 31(3), 292–309.
https://doi.org/10.1080/08870446.2015.1085986
Thorne, N., Yip, A. K.-T., Bouman, W. P., Marshall, E., & Arcelus, J. (2019). The
terminology of identities between, outside and beyond the gender binary – a
systematic review. International Journal of Transgenderism, 20(2/3), 138–154.
https://doi.org/10.1080/15532739.2019.1640654
Thoroughgood, C. N., Sawyer, K. B., & Webster, J. R. (2020). Creating a trans-inclusive
workplace: how to make transgender employees feel valued at work. Harvard
Business Review, 98(2), 114.

101
Thoroughgood, C. N., Sawyer, K. B., & Webster, J. R. (2017). What lies beneath: how
paranoid cognition explains the relations between transgender employees'
perceptions of discrimination at work and their job attitudes and well-being.
Journal of Vocational Behavior, 103, 99–112.
https://doi.org/10.1016/j.jvb.2017.07.009
Thorpe, S., Tanner, A. E., & Hargons, C. N. (2022). Sexual identity factors and minority
stressors associated with healthcare stereotype threat and access to care among
Black sexual minority women. Journal of Gay & Lesbian Social Services, 1–21.
https://doi.org/10.1080/10538720.2022.2056398
To, M., Zhang, Q., Bradlyn, A., Getahun, D., Giammattei, S., Nash, R., Owen-Smith, A.,
Roblin, D., Silverberg, M., Tangpricha, V., Vupputuri, V., & Goodman, M.
(2020, October 17). Visual conformity with affirmed gender or “passing”: Its
distribution and association with depression and anxiety in a cohort of
transgender people. Journal of Sexual Medicine, 17(10), 2084–
2092. https://doi.org/10.1016/j.jsxm.2020.07.019Treharne, G. J., Blakey, A. G.,
Graham, K., Carrington, S. D., McLachlan, L. A., Withey-Rila, C., PearmanBeres,
L., & Anderson, L. (2021). Perspectives on expertise in teaching about
transgender healthcare: a focus group study with health professional programme
teaching staff and transgender community members. International Journal of
Transgender Health, 23(3), 334–354.
https://doi.org/10.1080/26895269.2020.1870189

102
Van Laar, C., Meeussen, L., Veldman, J., Van Grootel, S., Sterk, N., & Jacobs, C. (2019).
Coping with stigma in the workplace: understanding the role of threat regulation,
supportive factors, and potential hidden costs. Frontiers in Psychology, 1–21.
https://doi.org/10.3389/fpsyg.2019.01879
Vincent, B. (2019). Breaking down barriers and binaries in trans healthcare: the
validation of non-binary people. International Journal of
Transgenderism, 20(2/3), 132–137.
https://doi.org/10.1080/15532739.2018.1534075
Wagner, T. L., Kitzie, V. L., & Lookingbill, V. (2022). Transgender and nonbinary
individuals and ICT-driven information practices in response to transexclusionary
healthcare systems: a qualitative study. Journal of the American Medical
Informatics Association, 29(2), 239–248. https://doi.org/10.1093/jamia/ocab234
Wesp, L. M., Malcoe, L. H., Elliott, A., & Poteat, T. (2019). Intersectionality research for
transgender health justice: a theory-driven conceptual framework for structural
analysis of transgender health inequities. Transgender Health, 4(1), 287–296.
https://doi.org/10.1089/trgh.2019.0039
Westbrook, L., & Schlit, K. (2014). Transgender people, gender panics, and the
maintenance of the sex/gender/sexuality system. Gender & Society, 28(1), 32-57.
https://doi.org/10.1177/0891243213508008
Whipple, K. (2021). The SAGE Encyclopedia of Trans Studies. (Vols. 1-2). SAGE
Publications.https://dx.doi.org/10.4135/9781544393858
White, H., & Sabarwal, S. (2014). Quasi-experimental design and methods
(Methodological Briefs: Impact Evaluation 8). UNICEF Office of

103
Research.Wichinski, K. A. (2015). Providing culturally proficient care for
transgender. Nursing, 45(2), 58–63.
https://doi.org/10.1097/01.NURSE.0000456370.79660.f8
Willging, C., Gunderson, L., Shattuck, D., Sturm, R., Lawyer, A., & Crandall, C. (2019).
Structural competency in emergency medicine services for transgender and gender
non-conforming patients. Social Science & Medicine, 222, 67–75.
https://doi.org/10.1016/j.socscimed.2018.12.031
Witt, H., & Medina-Martinez, K. (2022). Transgender rights & the urgent need for social
work advocacy. Social Work in Public Health, 37(1), 28–32.
https://doi.org/10.1080/19371918.2021.1970685
Wootton, A. R. (2024). To reduce sexual minority health care disparities, advocate for
expanded health insurance coverage and LGBTQ+ rights. American Journal of
Public Health, 114(1), 12–14. https://doi.org/10.2105/AJPH.2023.307513
Abdou, C. M., Fingerhut, A. W., Jackson, J. S., & Wheaton, F. (2016). Healthcare
stereotype threat in older adults in the health and retirement study. American
Journal of Preventive Medicine, 50(2), 191–198.
https://doi.org/10.1016/j.amepre.2015.07.034
Adegoke, A.O. (2018). On the Effects of Nonlinearity Between Variables on the
Correlation Coefficient. [University of Regina].
Arayasirikul, S., & Wilson, E. C. (2019). Spilling the t on trans-misogyny and
microaggressions: An intersectional oppression and social process among trans
women. Journal of Homosexuality, 66(10), 1415–1438.

104
https://doi.org/10.1080/00918369.2018.1542203
Asamoah, M. K. (2014). Re-examination of the limitations associated with correlational
research. Journal of Educational Research and Reviews, 2(4), 45–52.
Baboolall, D., Greenberg, S., Obeid, M., & Zucker, J. (2022). Being transgender at work.
McKinsey Quarterly, 1, 1–18.
Blackwell, C. W., Diaz-Cruz, A., & Yan, X. (2020). Equality and quality: The relationship
between Magnet® status and healthcare organizational commitment to lesbian,
gay, bisexual, and transgender equality. Journal of Social Service
Research, 46(5), 705–712. https://doi.org/10.1080/01488376.2019.1645796
Blazucki, S. (2023). The Equal Rights Amendment and the Equality Act: Closing Gaps
Post-Bostock for Sexual Orientation and Gender Identity Minorities. University of
the District of Columbia Law Review, 26 (1), Article 4.
Boe, J. L., Ellis, E. M., Sharstrom, K. A., & Gale, J. E. (2020). Disrupting cisnormativity,
transnormativity, and transmisogyny in healthcare: Advancing trans inclusive
practices for medical family therapists. Journal of Feminist Family Therapy,
32(3/4), 157–175. https://doi.org/10.1080/08952833.2020.1848051
Boot-Haury, J. W. (2023). A preliminary study of intensive transgender-specific cultural
competency training: Implications for social workers and psychologists who work
with rural transgender clients. Journal of Gay & Lesbian Social Services, 1–27.
https://doi.org/10.1080/10538720.2023.2266399

105
Brothers, K., Rivera, S., Cadigan, R., Sharp, R., & Goldenberg, A. (2019). A Belmont
reboot: Building a normative foundation for human research in the 21st century.
Journal of Law, Medicine & Ethics, 47(1), 165-172.
https://doi.org/10.1177/1073110519840497
Burgess, D. J., Warren, J., Phelan, S., Dovidio, J., & van Ryn, M. (2010). Stereotype
threat and health disparities: What medical educators and future physicians need
to know. Journal of General Internal Medicine, 25 Suppl 2(Suppl 2), S169–S177.
https://doi.org/10.1007/s11606-009-1221-4
Cabacungan, A., Lee, J., Chaney, B., & Averett, P. (2019). Does gender minority
professional experience impact employment discrimination? Two résumé
experiments. Journal of Youth Development, 14(4), 267–284.
https://doi.org/10.5195/jyd.2019.829
Canvin, L., Twist, J., & Solomons, W. (2023). “I don’t want to say the wrong thing”:
Mental health professionals’ narratives of feeling inadequately skilled when
working with gender diverse adults. Psychology & Sexuality, 14(2), 337–350.
https://doi.org/10.1080/19419899.2022.2118070
Castañeda, E., & Smith, C. (2023). Conducting research with marginalized populations:
Methodological, ethical, and IRB considerations. Journal of Applied Social
Sciences (19367244), 17(1), 111–131.
https://doi.org/10.1177/19367244221141326
Casey, L. S., Reisner, S. L., Findling, M. G., Blendon, R. J., Benson, J. M., Sayde, J. M.,
& Miller, C. (2019). Discrimination in the United States: Experiences of lesbian,
gay, bisexual, transgender, and queer Americans. Health Services Research, 54,

106
1454–1466. https://doi.org/10.1111/1475-6773.13229
Chirkov, V., & Anderson, J. (2018). Statistical positivism versus critical scientific realism
A comparison of two paradigms for motivation research: Part 1 A philosophical
and empirical analysis of statistical positivism. Theory &
Psychology, 28(6), 712–736. https://doi.org/10.1177/0959354318804670
Creswell, J. W., & Creswell, J. D. (2018). Research design: Qualitative, quantitative, and
mixed methods approaches. (5th ed.). SAGE Publications, Inc.
Dahlen, S. (2020). De-sexing the medical record? An examination of sex versus gender
identity in the general medical council’s trans healthcare ethical advice. New
bioethics, 26(1), 38–52. https://doi.org/10.1080/20502877.2020.1720429
Davidson, S., & Halsall, J. (2016). Gender inequality: Nonbinary transgender people in
the workplace. Cogent Social Sciences, 2(1), N.PAG.
https://doi.org/10.1080/23311886.2016.1236511
Davidson, S. (2016, August 16). Gender inequality: Nonbinary transgender people in the
workplace. Cogent Social Sciences, Volume 2, Issue 1.
https://www.tandfonline.com/doi/full/10.1080/23311886.2016.1236511
DiPalma, L. M. (2021). Gender and sexual orientation in the workplace. Research
Starters: Sociology.
Dixon, J., & Dougherty, D. S. (2014). A language convergence/meaning divergence
analysis exploring how LGBTQ and single employees manage traditional family
expectations in the workplace. Journal of Applied Communication
Research, 42(1), 1–19. https://doi.org/10.1080/00909882.2013.847275

107
Doyle, D. M. (2022). Transgender identity: development, management and affirmation.
Current Opinion in Psychology, 48.
https://doi.org/10.1016/j.copsyc.2022.101467
Doyle, D. M., Begeny, C. T., Barreto, M., & Morton, T. A. (2021). Identity-related factors
protect well-being against stigma for transgender and gender nonconforming
people. Archives of Sexual Behavior, 50(7), 3191–3200.
https://doi.org/10.1007/s10508-021-02029-1
Elias, N. M. R. (2017). Constructing and implementing transgender policy for public
administration. Administration & Society, 49(1), 20–47.
https://doi.org/10.1177/0095399716684888
Enders, F. T., Golembiewski, E. H., Pacheco-Spann, L. M., Allyse, M., Mielke, M. M., &
Balls-Berry, J. E. (2021). Building a framework for inclusion in health services
research: Development of and pre-implementation faculty and staff attitudes
toward the Diversity, Equity, and Inclusion (DEI) plan at Mayo Clinic. Journal of
Clinical & Translational Science, 5(1), 1–10. https://doi.org/10.1017/cts.2020.575
Flynn, M. K., & Bhambhani, Y. (2021). Internalized transphobia, nondisclosure of gender
identity, and life satisfaction among transgender and non-binary adults:
The moderating roles of psychological flexibility and inflexibility. Journal of
Contextual Behavioral Science, 20, 194–201.
https://doi.org/10.1016/j.jcbs.2021.04.008
Frankfort-Nachmias, C., Leon-Guerrero, A., Davis, G. (2021). Social statistics for a
diverse society (9th ed.). SAGE Publications, Inc.

108
Freedman, D. A. (2005). Statistical Models: Theory and Practice. Cambridge University
Press.
Friesen, P., Kearns, L., Redman, B., & Caplan, A. L. (2017). Rethinking the Belmont
Report? American Journal of Bioethics, 17(7), 15–21.
https://doi.org/10.1080/15265161.2017.1329482
Galupo, M. P., & Resnick, C. A. (2016). Experiences of LGBT microaggressions in the
workplace: Implications for policy. In T. Köllen (Ed.), Sexual orientation and
transgender issues in organizations (pp. 271-287).
Springer. https://doi.org/10.1007/978-3-319-29623-4_16
Ghosh, B. (2022). State, citizenship and gender-variant communities in India. Citizenship
Studies, 26(2), 127–145. https://doi.org/10.1080/13621025.2021.2024147
Giffort, D. M., & Underman, K. (2016). The relationship between medical education and
trans health disparities: a call to research. Sociology Compass, 10(11), 999–1013.
https://doi.org/10.1111/soc4.12432
Goldbach, C., Knutson, D., & Kler, S. (2021). The SAGE Encyclopedia of Trans Studies
(Vols. 1–2). SAGE Publications, Inc. https://doi.org/10.4135/9781544393858
Goldenberg, T., Reisner, S. L., Harper, G. W., Gamarel, K. E., & Stephenson, R. (2020).
State policies and healthcare use among transgender people in the U.S. American
Journal of Preventive Medicine, 59(2), 247–259.
https://doi.org/10.1016/j.amepre.2020.01.030
Goszkowicz, K., & Davis, P. (2023). Reducing Adult transgender barriers to care in the
emergency department: strategies to improve policies and practices. Advanced

109
Emergency Nursing Journal, 45(1), 3–10.
https://doi.org/10.1097/TME.0000000000000446
Green, E. & Mauer, L. (2015). Glossary of transgender terms, The Teaching Transgender
Toolkit. Second Edition, 53-56.
Hasan, M. N. (2016). Positivism: to what extent does it aid our understanding of the
contemporary social world? Quality & Quantity, 50(1), 317–325.
https://doi.org/10.1007/s11135-014-0150-4
Hazra, A., & Gogtay, N. (2016). Biostatistics Series Module 6: Correlation and Linear
Regression. Indian Journal of Dermatology, 61(6), 593–601.
https://doi.org/10.4103/0019-5154.193662
Herman, J., Flores, A., & O’Neill, K. (2022, June). How many adults and youth identify
as transgender in the United States? UCLA School of Law Williams Institute.
https://williamsinstitute.law.ucla.edu/wp-content/uploads/Trans-Pop-Update-
Jun2022.pdf
Hossain, M., Atif, M., Ahmed, A., & Mia, L. (2020). Do LGBT workplace diversity
policies create value for firms? Journal of Business Ethics, 167(4), 775–791.
https://doi.org/10.1007/s10551-019-04158-z
Huffman, A. H., Mills, M. J., Howes, S. S., & Albritton, M. D. (2021). Workplace support
and affirming behaviors: moving toward a transgender, gender diverse, and non-
binary friendly workplace. International Journal of Transgender
Health, 22(3), 225–242. https://doi.org/10.1080/26895269.2020.1861575

110
Hughto, J. M. W., Gunn, H. A., Rood, B. A., & Pantalone, D. W. (2020). Social and
medical gender affirmation experiences are inversely associated with mental
health problems in a U.S. non-probability sample of transgender adults. archives
of sexual behavior, 49(7), 2635–2647. https://doi.org/10.1007/s10508-020-01655-
5
Human Rights Campaign Foundation. (2022). Health equality index: promoting equitable
and inclusive care for LGBTQ+ patients and their families. Washington, DC.
Johnson, A. H., Hillb, I., Beach-Ferrara, J., Rogers, B. A., & Bradford, A. (2020).
Common barriers to healthcare for transgender people in the U.S.
Southeast. International Journal of Transgender Health, 21(1), 70–78.
https://doi.org/10.1080/15532739.2019.1700203
Kanamori, Y., & Cornelius-White, J. H. D. (2016). Big changes, but are they big enough?
Healthcare professionals’ attitudes toward transgender persons. International
Journal of Transgenderism, 17(3/4), 165–175.
https://doi.org/10.1080/15532739.2016.1232628
Kattari, S. K., Bakko, M., Hecht, H. K., & Kattari, L. (2020). Correlations between
healthcare provider interactions and mental health among transgender and
nonbinary adults. SSM: Population Health, 10.
https://doi.org/10.1016/j.ssmph.2019.100525
Katz-Wise, S. L., Boskey, E. R., Godwin, E. G., Thomson, K., Post, J., & Gordon, A. R.
(2022). “We’re moving in the right direction. Still a long way to go”: Experiences
and perceptions of the climate for LGBTQ+ employees at a pediatric hospital.

111
Journal of Homosexuality, 69(13), 2286–2304.
https://doi.org/10.1080/00918369.2021.1938468
Khaikin, C. & Uttley, L. (2016) Growth of catholic hospitals and health systems: 2016
update of the miscarriage of medicine report. Merger Watch.
http://static1.1.sqspcdn.com/static/f/816571/27061007/1465224862580/MW_Upd
ate-2016-
MiscarrOfMedicinereport.pdf?token=rf3rsQaaCVCzLV9hKOIHuFcaWiU%3D.
King, W. M., & Gamarel, K. E. (2021). A scoping review examining social and legal
gender affirmation and health among transgender populations. Transgender
Health, 6(1), 5–22. https://doi.org/10.1089/trgh.2020.0025
Kleintop, L. K. (2019). When transgender employees come out: perceived support and
cultural change in the transition process. Journal of Business Diversity, 19(5), 55–
67. https://doi.org/10.33423/jbd.v19i5.2645
Koch, J. M., McLachlan, C., Victor, C. J., Westcott, J., & Yager, C. (2020). The cost of
being transgender: where socio-economic status, global health care systems, and gender
identity intersect. Psychology & Sexuality, 11(1–2), 103–119.
https://doi.org/10.1080/19419899.2019.1660705
Krueger, E. A., Divsalar, S., Luhur, W., Choi, S. K., & Meyer, I. H. (2020). TransPop -
U.S. Transgender Population Health Survey (Methodology and Technical Notes).
Los Angeles, CA: The Williams Institute. Retrieved from:
https://www.transpop.org/s/TransPop-Survey-Methods-v18-FINAL-copy.pdf

112
Lakens, D., & Caldwell, A. R. (2021). Simulation-based power analysis for factorial
analysis of variance designs. Advances in Methods and Practices in Psychological
Science. https://doi.org/10.1177/2515245920951503
Leppel, K. (2016). The labor force status of transgender men and women. International
Journal of Transgenderism, 17(3/4), 155–164.
https://doi.org/10.1080/15532739.2016.1236312
Leppel, K. (2021). Transgender men and women in 2015: employed, unemployed, or not
in the labor force. Journal of Homosexuality, 68(2), 203–229.
https://doi.org/10.1080/00918369.2019.1648081
Lerner, J. E., Martin, J. I., & Gorsky, G. S. (2021). More than an apple a day: factors
associated with avoidance of doctor visits among transgender, gender
nonconforming, and nonbinary people in the USA. Sexuality Research & Social
Policy: Journal of NSRC, 18(2), 409–426. https://doi.org/10.1007/s13178-020-
00469-3
Liu, M., Sandhu, Keuroghlian, A, (2022, July 28). Achieving the triple aim for sexual and
gender minorities. The New England Journal of Medicine, 2022; 387:294-297. http://doi/
10.1056/NEJMp2204569
McGregor, B., Belton, A., Henry, T. L., Wrenn, G., & Holden, K. B. (2019). Improving
behavioral health equity through cultural competence training of health care
providers. Ethnicity & Disease, 29, 359–364.
https://doi.org/10.18865/ed.29.S2.359

113
McNulty, Y., McPhail, R., Inversi, C., Dundon, T., & Nechanska, E. (2018). Employee
voice mechanisms for lesbian, gay, bisexual and transgender expatriation: the role
of Employee-Resource Groups (ERGs) and allies. International Journal of
Human Resource Management, 29(5), 829–856.
https://doi.org/10.1080/09585192.2017.1376221
Meyer, H. (2016). Dignity’s transgender bias case could signal more religious freedom
clashes. Modern Healthcare, 46(33), 10–11.
Meyer, I. (2021) TransPop, United States, 2016-2018. Interuniversity Consortium for
Political and Social Research. https://doi.org/10.3886/ICPSR37938.v1
Meyer, I. H., Wilson, B. D. M., & O'Neill, K. (2021). LGBTQ people in the US: Select
findings from the generations and TransPop studies. Williams Institute, UCLA
School of Law.
Mizock, L., Woodrum, T. D., Riley, J., Sotilleo, E. A., Yuen, N., & Ormerod, A.
J. (2017). Coping with transphobia in employment: strategies used by transgender
and gender-diverse people in the United States. International Journal of
Transgenderism, 18(3), 282–294.
https://doi.org/10.1080/15532739.2017.1304313
Nadal, K. L., Whitman, C. N., Davis, L. S., Erazo, T., & Davidoff, K. C. (2016).
Microaggressions toward lesbian, gay, bisexual, transgender, queer, and
genderqueer people: a review of the literature. Journal of Sex Research, 53(4/5),
488–508. https://doi.org/10.1080/00224499.2016.1142495

114
Newman, C. E., Prankumar, S. K., Cover, R., Rasmussen, M. L., Marshall, D., &
Aggleton, P. (2021). Inclusive health care for LGBTQ+ youth: support, belonging,
and inclusivity labour. Critical Public Health, 31(4), 441–450.
https://doi.org/10.1080/09581596.2020.1725443
Owens, B., Mills, S., Lewis, N., & Guta, A. (2022). Work-related stressors and mental
health among LGBTQ workers: Results from a cross-sectional survey. PLoS
ONE, 17(10), 1–14. https://doi.org/10.1371/journal.pone.0275771
Parr, N. J., & Howe, B. G. (2020). Factors associated with frequency of gender identity
non-affirmation microaggressions among transgender persons. Culture, Health &
Sexuality. https://doi.org/10.1080/13691058.2020.1755454
Perales, F., Ablaza, C., Tomaszewski, W., & Emsen-Hough, D. (2021). You, me, and
them: understanding employees’ use of trans-affirming language within the
workplace. Sexuality Research & Social Policy: A Journal of the NSRC.
https://doi.org/10.1007/s13178-021-00592-9
Perone, A. K. (2020). Protecting health care for transgender older adults amidst a
backlash of US federal policies. Journal of Gerontological Social Work, 63(8),
743–752. https://doi.org/10.1080/01634372.2020.1808139
Petchko, K. (2018). How to write about economics and public policy. Academic Press,
271-300. https://doi.org/10.1016/B978-0-12-813010-0.00014-4.
Piegza, M., & Główczyński, P. (2022). Minority stress and selected mental disorders in
people with gender dysphoria and gender incongruence – a narrative review.
Medycyna Pracy, 73(2), 163–172.
https://doi.org/10.13075/mp.5893.01198

115
Reisner, S. L., Gamarel, K. E., Mizock, L., White Hughto, J. M., Keuroghlian, A. S., &
Pachankis, J. E. (2016). Discriminatory experiences associated with posttraumatic
stress disorder symptoms among transgender adults. Journal of Counseling
Psychology, 63(5), 509–519. https://doi.org/10.1037/cou0000143
Reisner, S. L., & Hughto, J. M. W. (2019). Comparing the health of non-binary and
binary transgender adults in a statewide non-probability sample. PLoS
ONE, 14(8), 1–20. https://doi.org/10.1371/journal.pone.0221583
Reisner, S. L., Hughto, J. M. W., Dunham, E. E., Heflin, K. J., Begenyi, J. B. G., Coffey,
E. J., & Cahill, S. (2015). Legal protections in public accommodations settings: a
critical public health issue for transgender and gender-nonconforming people.
Milbank Quarterly, 93(3), 484–515. https://doi.org/10.1111/1468-
0009.12127
Reisner, S. L., Moore, C. S., Asquith, A., Pardee, D. J., & Mayer, K. H. (2020). Gender
non-affirmation from cisgender male partners: development and validation of a
brief stigma scale for HIV research with transgender men who have sex with men
(Trans MSM). AIDS & Behavior, 24(1), 331–343. https://doi.org/10.1007/s10461-
019-02749-5
Robinson, M. (2020). Two-spirit identity in a time of gender fluidity. Journal of
Homosexuality, 67(12), 1675–1690.
https://doi.org/10.1080/00918369.2019.1613853
Rood, B. A., Puckett, J. A., Reisner, S. L., Maroney, M. R., Berman, A. K., & Pantalone,
D. W. (2017). Identity concealment in transgender adults: A qualitative assessment
of minority stress and gender affirmation. American Journal of

116
Orthopsychiatry, 87(6), 704–713. https://doi.org/10.1037/ort0000303
Rosich, Gina R. (2020). Sexual citizenship theory and employment discrimination among
transgender-identified people. Societies, 10(1), 17.
https://doi.org/10.3390/soc10010017
Rouse, M., Jr., & Hamilton, E. (2021). Rethinking sex and the brain: how to create an
inclusive discourse in neuroscience. Mind, Brain, and Education, 15(2), 163–167. Rusow,
J. A., Hidalgo, M. A., Calvetti, S., Quint, M., Wu, S., Bray, B. C., & Kipke, M.
D. (2022). Health and service utilization among a sample of gender-diverse youth
of color: the TRUTH study. BMC Public Health, 22(1), 1–13.
https://doi.org/10.1186/s12889-022-14585-9
Saunders, R. K., Carr, D. C., & Burdette, A. M. (2023). Health care stereotype threat and
sexual and gender minority well-being. journal of health & social behavior, 1.
https://doi.org/10.1177/00221465231205549
Sawyer, K., & Thoroughgood, C. (2017). Gender non-conformity and the modern
workplace: new frontiers in understanding and promoting gender identity
expression at work. Organizational Dynamics, 46(1), 1–8.
https://doi.org/10.1016/j.orgdyn.2017.01.001
Scott, D., Pereira, N. M., Harrison, S. E., Zarwell, M., Sanasi-Bhola, K., & Poteat, T.
(2021). “In the Bible Belt:” The role of religion in HIV care and prevention for
transgender people in the United States south. Health & Place, 70, N.PAG.
https://doi.org/10.1016/j.healthplace.2021.1

117
Seelman, K. L., & Poteat, T. (2020). Strategies used by transmasculine and non-binary
adults assigned female at birth to resist transgender stigma in healthcare.
International Journal of Transgender Health, 21(3), 350–365.
https://doi.org/10.1080/26895269.2020.1781017
Serano, J. (2021). The SAGE Encyclopedia of Trans Studies (Vols. 1-2). SAGE
Publications. https://dx.doi.org/10.4135/9781544393858
Sevelius J. (2013). Gender affirmation: a framework for conceptualizing risk behavior
among transgender women of color. Sex Roles. 68(11–12):675–689.
https://doi.org/10.1007/s11199-012-0216-5
Sherman, B., Kelly, R., & Payne-Foster, P. (2021). Integrating workforce health into
employer diversity, equity, and inclusion efforts. American Journal of Health
Promotion, 35(5), 609–612. https://doi.org/10.1177/0890117120983288
Siad, F. & Rabi, D. (2021). Harassment in the field of medicine: cultural barriers to
psychological safety. CJC Open, 3(12), S174–S179.
https://doi.org/10.1016/j.cjco.2021.08.018
Smart, B. D., Mann-Jackson, L., Alonzo, J., Tanner, A. E., Garcia, M., Refugio Aviles,
L., & Rhodes, S. D. (2022). Transgender women of color in the US South: A
qualitative study of social determinants of health and healthcare perspectives.
International Journal of Transgender Health, 23(1–2), 164–177.
https://doi.org/10.1080/26895269.2020.1848691
Stewart, C. (2020). The future is queer kids: Queering the homonormative temporalities
of same-sex marriage. Politics, 40(3), 265–280.
https://doi.org/10.1177/0263395719872595

118
Stroumsa, D., Shires, D. A., Richardson, C. R., Jaffee, K. D., & Woodford, M. R. (2019).
Transphobia rather than education predicts provider knowledge of transgender
health care. Medical Education, 53(4), 398–407.
https://doi.org/10.1111/medu.13796
Szemanski, A. (2020). When trans rights are disability rights: the promises and perils of
seeking gender dysphoria coverage under the Americans with disabilities act.
Harvard Journal of Law & Gender, 43(1), 137–168.
Taber, J. M., Howell, J. L., Emanuel, A. S., Klein, W. M. P., Ferrer, R. A., & Harris, P.
R. (2016). Associations of spontaneous self-affirmation with health care
experiences and health information seeking in a national survey of US adults.
Psychology & Health, 31(3), 292–309.
https://doi.org/10.1080/08870446.2015.1085986
Thorne, N., Yip, A. K.-T., Bouman, W. P., Marshall, E., & Arcelus, J. (2019). The
terminology of identities between, outside and beyond the gender binary – a
systematic review. International Journal of Transgenderism, 20(2/3), 138–154.
https://doi.org/10.1080/15532739.2019.1640654
Thoroughgood, C. N., Sawyer, K. B., & Webster, J. R. (2020). Creating a trans-inclusive
workplace: how to make transgender employees feel valued at work. Harvard
Business Review, 98(2), 114.
Thoroughgood, C. N., Sawyer, K. B., & Webster, J. R. (2017). What lies beneath: how
paranoid cognition explains the relations between transgender employees'
perceptions of discrimination at work and their job attitudes and well-being.

119
Journal of Vocational Behavior, 103, 99–112.
https://doi.org/10.1016/j.jvb.2017.07.009
Thorpe, S., Tanner, A. E., & Hargons, C. N. (2022). Sexual identity factors and minority
stressors associated with healthcare stereotype threat and access to care among
Black sexual minority women. Journal of Gay & Lesbian Social Services, 1–21.
https://doi.org/10.1080/10538720.2022.2056398
To, M., Zhang, Q., Bradlyn, A., Getahun, D., Giammattei, S., Nash, R., Owen-Smith, A.,
Roblin, D., Silverberg, M., Tangpricha, V., Vupputuri, V., & Goodman, M.
(2020, October 17). Visual conformity with affirmed gender or “passing”: Its
distribution and association with depression and anxiety in a cohort of
transgender people. Journal of Sexual Medicine, 17(10), 2084–
2092. https://doi.org/10.1016/j.jsxm.2020.07.019Treharne, G. J., Blakey, A. G.,
Graham, K., Carrington, S. D., McLachlan, L. A., Withey-Rila, C., PearmanBeres,
L., & Anderson, L. (2021). Perspectives on expertise in teaching about
transgender healthcare: a focus group study with health professional programme
teaching staff and transgender community members. International Journal of
Transgender Health, 23(3), 334–354.
https://doi.org/10.1080/26895269.2020.1870189
Van Laar, C., Meeussen, L., Veldman, J., Van Grootel, S., Sterk, N., & Jacobs, C. (2019).
Coping with stigma in the workplace: understanding the role of threat regulation,
supportive factors, and potential hidden costs. Frontiers in Psychology, 1–21.
https://doi.org/10.3389/fpsyg.2019.01879

120
Vincent, B. (2019). Breaking down barriers and binaries in trans healthcare: the
validation of non-binary people. International Journal of
Transgenderism, 20(2/3), 132–137.
https://doi.org/10.1080/15532739.2018.1534075
Wagner, T. L., Kitzie, V. L., & Lookingbill, V. (2022). Transgender and nonbinary
individuals and ICT-driven information practices in response to transexclusionary
healthcare systems: a qualitative study. Journal of the American Medical
Informatics Association, 29(2), 239–248. https://doi.org/10.1093/jamia/ocab234
Wesp, L. M., Malcoe, L. H., Elliott, A., & Poteat, T. (2019). Intersectionality research for
transgender health justice: a theory-driven conceptual framework for structural
analysis of transgender health inequities. Transgender Health, 4(1), 287–296.
https://doi.org/10.1089/trgh.2019.0039
Westbrook, L., & Schlit, K. (2014). Transgender people, gender panics, and the
maintenance of the sex/gender/sexuality system. Gender & Society, 28(1), 32-57.
https://doi.org/10.1177/0891243213508008
Whipple, K. (2021). The SAGE Encyclopedia of Trans Studies. (Vols. 1-2). SAGE
Publications.https://dx.doi.org/10.4135/9781544393858
White, H., & Sabarwal, S. (2014). Quasi-experimental design and methods
(Methodological Briefs: Impact Evaluation 8). UNICEF Office of
Research.Wichinski, K. A. (2015). Providing culturally proficient care for
transgender. Nursing, 45(2), 58–63.
https://doi.org/10.1097/01.NURSE.0000456370.79660.f8

121
Willging, C., Gunderson, L., Shattuck, D., Sturm, R., Lawyer, A., & Crandall, C. (2019).
Structural competency in emergency medicine services for transgender and gender
non-conforming patients. Social Science & Medicine, 222, 67–75.
https://doi.org/10.1016/j.socscimed.2018.12.031
Witt, H., & Medina-Martinez, K. (2022). Transgender rights & the urgent need for social
work advocacy. Social Work in Public Health, 37(1), 28–32.
https://doi.org/10.1080/19371918.2021.1970685
Wootton, A. R. (2024). To reduce sexual minority health care disparities, advocate for
expanded health insurance coverage and LGBTQ+ rights. American Journal of
Public Health, 114(1), 12–14. https://doi.org/10.2105/AJPH.2023.307513
Abdou, C. M., Fingerhut, A. W., Jackson, J. S., & Wheaton, F. (2016). Healthcare
stereotype threat in older adults in the health and retirement study. American
Journal of Preventive Medicine, 50(2), 191–198.
https://doi.org/10.1016/j.amepre.2015.07.034
Adegoke, A.O. (2018). On the Effects of Nonlinearity Between Variables on the
Correlation Coefficient. [University of Regina].
Arayasirikul, S., & Wilson, E. C. (2019). Spilling the t on trans-misogyny and
microaggressions: An intersectional oppression and social process among trans
women. Journal of Homosexuality, 66(10), 1415–1438.
https://doi.org/10.1080/00918369.2018.1542203
Asamoah, M. K. (2014). Re-examination of the limitations associated with correlational
research. Journal of Educational Research and Reviews, 2(4), 45–52.

122
Baboolall, D., Greenberg, S., Obeid, M., & Zucker, J. (2022). Being transgender at work.
McKinsey Quarterly, 1, 1–18.
Blackwell, C. W., Diaz-Cruz, A., & Yan, X. (2020). Equality and quality: The relationship
between Magnet® status and healthcare organizational commitment to lesbian,
gay, bisexual, and transgender equality. Journal of Social Service
Research, 46(5), 705–712. https://doi.org/10.1080/01488376.2019.1645796
Blazucki, S. (2023). The Equal Rights Amendment and the Equality Act: Closing Gaps
Post-Bostock for Sexual Orientation and Gender Identity Minorities. University of
the District of Columbia Law Review, 26 (1), Article 4.
Boe, J. L., Ellis, E. M., Sharstrom, K. A., & Gale, J. E. (2020). Disrupting cisnormativity,
transnormativity, and transmisogyny in healthcare: Advancing trans inclusive
practices for medical family therapists. Journal of Feminist Family Therapy,
32(3/4), 157–175. https://doi.org/10.1080/08952833.2020.1848051
Boot-Haury, J. W. (2023). A preliminary study of intensive transgender-specific cultural
competency training: Implications for social workers and psychologists who work
with rural transgender clients. Journal of Gay & Lesbian Social Services, 1–27.
https://doi.org/10.1080/10538720.2023.2266399
Brothers, K., Rivera, S., Cadigan, R., Sharp, R., & Goldenberg, A. (2019). A Belmont
reboot: Building a normative foundation for human research in the 21st century.
Journal of Law, Medicine & Ethics, 47(1), 165-172.
https://doi.org/10.1177/1073110519840497

123
Burgess, D. J., Warren, J., Phelan, S., Dovidio, J., & van Ryn, M. (2010). Stereotype
threat and health disparities: What medical educators and future physicians need
to know. Journal of General Internal Medicine, 25 Suppl 2(Suppl 2), S169–S177.
https://doi.org/10.1007/s11606-009-1221-4
Cabacungan, A., Lee, J., Chaney, B., & Averett, P. (2019). Does gender minority
professional experience impact employment discrimination? Two résumé
experiments. Journal of Youth Development, 14(4), 267–284.
https://doi.org/10.5195/jyd.2019.829
Canvin, L., Twist, J., & Solomons, W. (2023). “I don’t want to say the wrong thing”:
Mental health professionals’ narratives of feeling inadequately skilled when
working with gender diverse adults. Psychology & Sexuality, 14(2), 337–350.
https://doi.org/10.1080/19419899.2022.2118070
Castañeda, E., & Smith, C. (2023). Conducting research with marginalized populations:
Methodological, ethical, and IRB considerations. Journal of Applied Social
Sciences (19367244), 17(1), 111–131.
https://doi.org/10.1177/19367244221141326
Casey, L. S., Reisner, S. L., Findling, M. G., Blendon, R. J., Benson, J. M., Sayde, J. M.,
& Miller, C. (2019). Discrimination in the United States: Experiences of lesbian,
gay, bisexual, transgender, and queer Americans. Health Services Research, 54,
1454–1466. https://doi.org/10.1111/1475-6773.13229
Chirkov, V., & Anderson, J. (2018). Statistical positivism versus critical scientific realism
A comparison of two paradigms for motivation research: Part 1 A philosophical
and empirical analysis of statistical positivism. Theory &

124
Psychology, 28(6), 712–736. https://doi.org/10.1177/0959354318804670
Creswell, J. W., & Creswell, J. D. (2018). Research design: Qualitative, quantitative, and
mixed methods approaches. (5th ed.). SAGE Publications, Inc.
Dahlen, S. (2020). De-sexing the medical record? An examination of sex versus gender
identity in the general medical council’s trans healthcare ethical advice. New
bioethics, 26(1), 38–52. https://doi.org/10.1080/20502877.2020.1720429
Davidson, S., & Halsall, J. (2016). Gender inequality: Nonbinary transgender people in
the workplace. Cogent Social Sciences, 2(1), N.PAG.
https://doi.org/10.1080/23311886.2016.1236511
Davidson, S. (2016, August 16). Gender inequality: Nonbinary transgender people in the
workplace. Cogent Social Sciences, Volume 2, Issue 1.
https://www.tandfonline.com/doi/full/10.1080/23311886.2016.1236511
DiPalma, L. M. (2021). Gender and sexual orientation in the workplace. Research
Starters: Sociology.
Dixon, J., & Dougherty, D. S. (2014). A language convergence/meaning divergence
analysis exploring how LGBTQ and single employees manage traditional family
expectations in the workplace. Journal of Applied Communication
Research, 42(1), 1–19. https://doi.org/10.1080/00909882.2013.847275
Doyle, D. M. (2022). Transgender identity: development, management and affirmation.
Current Opinion in Psychology, 48.
https://doi.org/10.1016/j.copsyc.2022.101467

125
Doyle, D. M., Begeny, C. T., Barreto, M., & Morton, T. A. (2021). Identity-related factors
protect well-being against stigma for transgender and gender nonconforming
people. Archives of Sexual Behavior, 50(7), 3191–3200.
https://doi.org/10.1007/s10508-021-02029-1
Elias, N. M. R. (2017). Constructing and implementing transgender policy for public
administration. Administration & Society, 49(1), 20–47.
https://doi.org/10.1177/0095399716684888
Enders, F. T., Golembiewski, E. H., Pacheco-Spann, L. M., Allyse, M., Mielke, M. M., &
Balls-Berry, J. E. (2021). Building a framework for inclusion in health services
research: Development of and pre-implementation faculty and staff attitudes
toward the Diversity, Equity, and Inclusion (DEI) plan at Mayo Clinic. Journal of
Clinical & Translational Science, 5(1), 1–10. https://doi.org/10.1017/cts.2020.575
Flynn, M. K., & Bhambhani, Y. (2021). Internalized transphobia, nondisclosure of gender
identity, and life satisfaction among transgender and non-binary adults:
The moderating roles of psychological flexibility and inflexibility. Journal of
Contextual Behavioral Science, 20, 194–201.
https://doi.org/10.1016/j.jcbs.2021.04.008
Frankfort-Nachmias, C., Leon-Guerrero, A., Davis, G. (2021). Social statistics for a
diverse society (9th ed.). SAGE Publications, Inc.
Freedman, D. A. (2005). Statistical Models: Theory and Practice. Cambridge University
Press.
Friesen, P., Kearns, L., Redman, B., & Caplan, A. L. (2017). Rethinking the Belmont

126
Report? American Journal of Bioethics, 17(7), 15–21.
https://doi.org/10.1080/15265161.2017.1329482
Galupo, M. P., & Resnick, C. A. (2016). Experiences of LGBT microaggressions in the
workplace: Implications for policy. In T. Köllen (Ed.), Sexual orientation and
transgender issues in organizations (pp. 271-287).
Springer. https://doi.org/10.1007/978-3-319-29623-4_16
Ghosh, B. (2022). State, citizenship and gender-variant communities in India. Citizenship
Studies, 26(2), 127–145. https://doi.org/10.1080/13621025.2021.2024147
Giffort, D. M., & Underman, K. (2016). The relationship between medical education and
trans health disparities: a call to research. Sociology Compass, 10(11), 999–1013.
https://doi.org/10.1111/soc4.12432
Goldbach, C., Knutson, D., & Kler, S. (2021). The SAGE Encyclopedia of Trans Studies
(Vols. 1–2). SAGE Publications, Inc. https://doi.org/10.4135/9781544393858
Goldenberg, T., Reisner, S. L., Harper, G. W., Gamarel, K. E., & Stephenson, R. (2020).
State policies and healthcare use among transgender people in the U.S. American
Journal of Preventive Medicine, 59(2), 247–259.
https://doi.org/10.1016/j.amepre.2020.01.030
Goszkowicz, K., & Davis, P. (2023). Reducing Adult transgender barriers to care in the
emergency department: strategies to improve policies and practices. Advanced
Emergency Nursing Journal, 45(1), 3–10.
https://doi.org/10.1097/TME.0000000000000446
Green, E. & Mauer, L. (2015). Glossary of transgender terms, The Teaching Transgender

127
Toolkit. Second Edition, 53-56.
Hasan, M. N. (2016). Positivism: to what extent does it aid our understanding of the
contemporary social world? Quality & Quantity, 50(1), 317–325.
https://doi.org/10.1007/s11135-014-0150-4
Hazra, A., & Gogtay, N. (2016). Biostatistics Series Module 6: Correlation and Linear
Regression. Indian Journal of Dermatology, 61(6), 593–601.
https://doi.org/10.4103/0019-5154.193662
Herman, J., Flores, A., & O’Neill, K. (2022, June). How many adults and youth identify
as transgender in the United States? UCLA School of Law Williams Institute.
https://williamsinstitute.law.ucla.edu/wp-content/uploads/Trans-Pop-Update-
Jun2022.pdf
Hossain, M., Atif, M., Ahmed, A., & Mia, L. (2020). Do LGBT workplace diversity
policies create value for firms? Journal of Business Ethics, 167(4), 775–791.
https://doi.org/10.1007/s10551-019-04158-z
Huffman, A. H., Mills, M. J., Howes, S. S., & Albritton, M. D. (2021). Workplace support
and affirming behaviors: moving toward a transgender, gender diverse, and non-
binary friendly workplace. International Journal of Transgender
Health, 22(3), 225–242. https://doi.org/10.1080/26895269.2020.1861575
Hughto, J. M. W., Gunn, H. A., Rood, B. A., & Pantalone, D. W. (2020). Social and
medical gender affirmation experiences are inversely associated with mental
health problems in a U.S. non-probability sample of transgender adults. archives
of sexual behavior, 49(7), 2635–2647. https://doi.org/10.1007/s10508-020-01655-

128
5
Human Rights Campaign Foundation. (2022). Health equality index: promoting equitable
and inclusive care for LGBTQ+ patients and their families. Washington, DC.
Johnson, A. H., Hillb, I., Beach-Ferrara, J., Rogers, B. A., & Bradford, A. (2020).
Common barriers to healthcare for transgender people in the U.S.
Southeast. International Journal of Transgender Health, 21(1), 70–78.
https://doi.org/10.1080/15532739.2019.1700203
Kanamori, Y., & Cornelius-White, J. H. D. (2016). Big changes, but are they big enough?
Healthcare professionals’ attitudes toward transgender persons. International
Journal of Transgenderism, 17(3/4), 165–175.
https://doi.org/10.1080/15532739.2016.1232628
Kattari, S. K., Bakko, M., Hecht, H. K., & Kattari, L. (2020). Correlations between
healthcare provider interactions and mental health among transgender and
nonbinary adults. SSM: Population Health, 10.
https://doi.org/10.1016/j.ssmph.2019.100525
Katz-Wise, S. L., Boskey, E. R., Godwin, E. G., Thomson, K., Post, J., & Gordon, A. R.
(2022). “We’re moving in the right direction. Still a long way to go”: Experiences
and perceptions of the climate for LGBTQ+ employees at a pediatric hospital.
Journal of Homosexuality, 69(13), 2286–2304.
https://doi.org/10.1080/00918369.2021.1938468
Khaikin, C. & Uttley, L. (2016) Growth of catholic hospitals and health systems: 2016
update of the miscarriage of medicine report. Merger Watch.

129
http://static1.1.sqspcdn.com/static/f/816571/27061007/1465224862580/MW_Upd
ate-2016-
MiscarrOfMedicinereport.pdf?token=rf3rsQaaCVCzLV9hKOIHuFcaWiU%3D.
King, W. M., & Gamarel, K. E. (2021). A scoping review examining social and legal
gender affirmation and health among transgender populations. Transgender
Health, 6(1), 5–22. https://doi.org/10.1089/trgh.2020.0025
Kleintop, L. K. (2019). When transgender employees come out: perceived support and
cultural change in the transition process. Journal of Business Diversity, 19(5), 55–
67. https://doi.org/10.33423/jbd.v19i5.2645
Koch, J. M., McLachlan, C., Victor, C. J., Westcott, J., & Yager, C. (2020). The cost of
being transgender: where socio-economic status, global health care systems, and gender
identity intersect. Psychology & Sexuality, 11(1–2), 103–119.
https://doi.org/10.1080/19419899.2019.1660705
Krueger, E. A., Divsalar, S., Luhur, W., Choi, S. K., & Meyer, I. H. (2020). TransPop -
U.S. Transgender Population Health Survey (Methodology and Technical Notes).
Los Angeles, CA: The Williams Institute. Retrieved from:
https://www.transpop.org/s/TransPop-Survey-Methods-v18-FINAL-copy.pdf
Lakens, D., & Caldwell, A. R. (2021). Simulation-based power analysis for factorial
analysis of variance designs. Advances in Methods and Practices in Psychological
Science. https://doi.org/10.1177/2515245920951503
Leppel, K. (2016). The labor force status of transgender men and women. International

130
Journal of Transgenderism, 17(3/4), 155–164.
https://doi.org/10.1080/15532739.2016.1236312
Leppel, K. (2021). Transgender men and women in 2015: employed, unemployed, or not
in the labor force. Journal of Homosexuality, 68(2), 203–229.
https://doi.org/10.1080/00918369.2019.1648081
Lerner, J. E., Martin, J. I., & Gorsky, G. S. (2021). More than an apple a day: factors
associated with avoidance of doctor visits among transgender, gender
nonconforming, and nonbinary people in the USA. Sexuality Research & Social
Policy: Journal of NSRC, 18(2), 409–426. https://doi.org/10.1007/s13178-020-
00469-3
Liu, M., Sandhu, Keuroghlian, A, (2022, July 28). Achieving the triple aim for sexual and
gender minorities. The New England Journal of Medicine, 2022; 387:294-297. http://doi/
10.1056/NEJMp2204569
McGregor, B., Belton, A., Henry, T. L., Wrenn, G., & Holden, K. B. (2019). Improving
behavioral health equity through cultural competence training of health care
providers. Ethnicity & Disease, 29, 359–364.
https://doi.org/10.18865/ed.29.S2.359
McNulty, Y., McPhail, R., Inversi, C., Dundon, T., & Nechanska, E. (2018). Employee
voice mechanisms for lesbian, gay, bisexual and transgender expatriation: the role
of Employee-Resource Groups (ERGs) and allies. International Journal of
Human Resource Management, 29(5), 829–856.
https://doi.org/10.1080/09585192.2017.1376221

131
Meyer, H. (2016). Dignity’s transgender bias case could signal more religious freedom
clashes. Modern Healthcare, 46(33), 10–11.
Meyer, I. (2021) TransPop, United States, 2016-2018. Interuniversity Consortium for
Political and Social Research. https://doi.org/10.3886/ICPSR37938.v1
Meyer, I. H., Wilson, B. D. M., & O'Neill, K. (2021). LGBTQ people in the US: Select
findings from the generations and TransPop studies. Williams Institute, UCLA
School of Law.
Mizock, L., Woodrum, T. D., Riley, J., Sotilleo, E. A., Yuen, N., & Ormerod, A.
J. (2017). Coping with transphobia in employment: strategies used by transgender
and gender-diverse people in the United States. International Journal of
Transgenderism, 18(3), 282–294.
https://doi.org/10.1080/15532739.2017.1304313
Nadal, K. L., Whitman, C. N., Davis, L. S., Erazo, T., & Davidoff, K. C. (2016).
Microaggressions toward lesbian, gay, bisexual, transgender, queer, and
genderqueer people: a review of the literature. Journal of Sex Research, 53(4/5),
488–508. https://doi.org/10.1080/00224499.2016.1142495
Newman, C. E., Prankumar, S. K., Cover, R., Rasmussen, M. L., Marshall, D., &
Aggleton, P. (2021). Inclusive health care for LGBTQ+ youth: support, belonging,
and inclusivity labour. Critical Public Health, 31(4), 441–450.
https://doi.org/10.1080/09581596.2020.1725443
Owens, B., Mills, S., Lewis, N., & Guta, A. (2022). Work-related stressors and mental
health among LGBTQ workers: Results from a cross-sectional survey. PLoS
ONE, 17(10), 1–14. https://doi.org/10.1371/journal.pone.0275771

132
Parr, N. J., & Howe, B. G. (2020). Factors associated with frequency of gender identity
non-affirmation microaggressions among transgender persons. Culture, Health &
Sexuality. https://doi.org/10.1080/13691058.2020.1755454
Perales, F., Ablaza, C., Tomaszewski, W., & Emsen-Hough, D. (2021). You, me, and
them: understanding employees’ use of trans-affirming language within the
workplace. Sexuality Research & Social Policy: A Journal of the NSRC.
https://doi.org/10.1007/s13178-021-00592-9
Perone, A. K. (2020). Protecting health care for transgender older adults amidst a
backlash of US federal policies. Journal of Gerontological Social Work, 63(8),
743–752. https://doi.org/10.1080/01634372.2020.1808139
Petchko, K. (2018). How to write about economics and public policy. Academic Press,
271-300. https://doi.org/10.1016/B978-0-12-813010-0.00014-4.
Piegza, M., & Główczyński, P. (2022). Minority stress and selected mental disorders in
people with gender dysphoria and gender incongruence – a narrative review.
Medycyna Pracy, 73(2), 163–172.
https://doi.org/10.13075/mp.5893.01198
Reisner, S. L., Gamarel, K. E., Mizock, L., White Hughto, J. M., Keuroghlian, A. S., &
Pachankis, J. E. (2016). Discriminatory experiences associated with posttraumatic
stress disorder symptoms among transgender adults. Journal of Counseling
Psychology, 63(5), 509–519. https://doi.org/10.1037/cou0000143
Reisner, S. L., & Hughto, J. M. W. (2019). Comparing the health of non-binary and
binary transgender adults in a statewide non-probability sample. PLoS
ONE, 14(8), 1–20. https://doi.org/10.1371/journal.pone.0221583

133
Reisner, S. L., Hughto, J. M. W., Dunham, E. E., Heflin, K. J., Begenyi, J. B. G., Coffey,
E. J., & Cahill, S. (2015). Legal protections in public accommodations settings: a
critical public health issue for transgender and gender-nonconforming people.
Milbank Quarterly, 93(3), 484–515. https://doi.org/10.1111/1468-
0009.12127
Reisner, S. L., Moore, C. S., Asquith, A., Pardee, D. J., & Mayer, K. H. (2020). Gender
non-affirmation from cisgender male partners: development and validation of a
brief stigma scale for HIV research with transgender men who have sex with men
(Trans MSM). AIDS & Behavior, 24(1), 331–343. https://doi.org/10.1007/s10461-
019-02749-5
Robinson, M. (2020). Two-spirit identity in a time of gender fluidity. Journal of
Homosexuality, 67(12), 1675–1690.
https://doi.org/10.1080/00918369.2019.1613853
Rood, B. A., Puckett, J. A., Reisner, S. L., Maroney, M. R., Berman, A. K., & Pantalone,
D. W. (2017). Identity concealment in transgender adults: A qualitative assessment
of minority stress and gender affirmation. American Journal of
Orthopsychiatry, 87(6), 704–713. https://doi.org/10.1037/ort0000303
Rosich, Gina R. (2020). Sexual citizenship theory and employment discrimination among
transgender-identified people. Societies, 10(1), 17.
https://doi.org/10.3390/soc10010017
Rouse, M., Jr., & Hamilton, E. (2021). Rethinking sex and the brain: how to create an
inclusive discourse in neuroscience. Mind, Brain, and Education, 15(2), 163–167. Rusow,
J. A., Hidalgo, M. A., Calvetti, S., Quint, M., Wu, S., Bray, B. C., & Kipke, M.

134
D. (2022). Health and service utilization among a sample of gender-diverse youth
of color: the TRUTH study. BMC Public Health, 22(1), 1–13.
https://doi.org/10.1186/s12889-022-14585-9
Saunders, R. K., Carr, D. C., & Burdette, A. M. (2023). Health care stereotype threat and
sexual and gender minority well-being. journal of health & social behavior, 1.
https://doi.org/10.1177/00221465231205549
Sawyer, K., & Thoroughgood, C. (2017). Gender non-conformity and the modern
workplace: new frontiers in understanding and promoting gender identity
expression at work. Organizational Dynamics, 46(1), 1–8.
https://doi.org/10.1016/j.orgdyn.2017.01.001
Scott, D., Pereira, N. M., Harrison, S. E., Zarwell, M., Sanasi-Bhola, K., & Poteat, T.
(2021). “In the Bible Belt:” The role of religion in HIV care and prevention for
transgender people in the United States south. Health & Place, 70, N.PAG.
https://doi.org/10.1016/j.healthplace.2021.1
Seelman, K. L., & Poteat, T. (2020). Strategies used by transmasculine and non-binary
adults assigned female at birth to resist transgender stigma in healthcare.
International Journal of Transgender Health, 21(3), 350–365.
https://doi.org/10.1080/26895269.2020.1781017
Serano, J. (2021). The SAGE Encyclopedia of Trans Studies (Vols. 1-2). SAGE
Publications. https://dx.doi.org/10.4135/9781544393858
Sevelius J. (2013). Gender affirmation: a framework for conceptualizing risk behavior
among transgender women of color. Sex Roles. 68(11–12):675–689.

135
https://doi.org/10.1007/s11199-012-0216-5
Sherman, B., Kelly, R., & Payne-Foster, P. (2021). Integrating workforce health into
employer diversity, equity, and inclusion efforts. American Journal of Health
Promotion, 35(5), 609–612. https://doi.org/10.1177/0890117120983288
Siad, F. & Rabi, D. (2021). Harassment in the field of medicine: cultural barriers to
psychological safety. CJC Open, 3(12), S174–S179.
https://doi.org/10.1016/j.cjco.2021.08.018
Smart, B. D., Mann-Jackson, L., Alonzo, J., Tanner, A. E., Garcia, M., Refugio Aviles,
L., & Rhodes, S. D. (2022). Transgender women of color in the US South: A
qualitative study of social determinants of health and healthcare perspectives.
International Journal of Transgender Health, 23(1–2), 164–177.
https://doi.org/10.1080/26895269.2020.1848691
Stewart, C. (2020). The future is queer kids: Queering the homonormative temporalities
of same-sex marriage. Politics, 40(3), 265–280.
https://doi.org/10.1177/0263395719872595
Stroumsa, D., Shires, D. A., Richardson, C. R., Jaffee, K. D., & Woodford, M. R. (2019).
Transphobia rather than education predicts provider knowledge of transgender
health care. Medical Education, 53(4), 398–407.
https://doi.org/10.1111/medu.13796
Szemanski, A. (2020). When trans rights are disability rights: the promises and perils of
seeking gender dysphoria coverage under the Americans with disabilities act.
Harvard Journal of Law & Gender, 43(1), 137–168.

136
Taber, J. M., Howell, J. L., Emanuel, A. S., Klein, W. M. P., Ferrer, R. A., & Harris, P.
R. (2016). Associations of spontaneous self-affirmation with health care
experiences and health information seeking in a national survey of US adults.
Psychology & Health, 31(3), 292–309.
https://doi.org/10.1080/08870446.2015.1085986
Thorne, N., Yip, A. K.-T., Bouman, W. P., Marshall, E., & Arcelus, J. (2019). The
terminology of identities between, outside and beyond the gender binary – a
systematic review. International Journal of Transgenderism, 20(2/3), 138–154.
https://doi.org/10.1080/15532739.2019.1640654
Thoroughgood, C. N., Sawyer, K. B., & Webster, J. R. (2020). Creating a trans-inclusive
workplace: how to make transgender employees feel valued at work. Harvard
Business Review, 98(2), 114.
Thoroughgood, C. N., Sawyer, K. B., & Webster, J. R. (2017). What lies beneath: how
paranoid cognition explains the relations between transgender employees'
perceptions of discrimination at work and their job attitudes and well-being.
Journal of Vocational Behavior, 103, 99–112.
https://doi.org/10.1016/j.jvb.2017.07.009
Thorpe, S., Tanner, A. E., & Hargons, C. N. (2022). Sexual identity factors and minority
stressors associated with healthcare stereotype threat and access to care among
Black sexual minority women. Journal of Gay & Lesbian Social Services, 1–21.
https://doi.org/10.1080/10538720.2022.2056398
To, M., Zhang, Q., Bradlyn, A., Getahun, D., Giammattei, S., Nash, R., Owen-Smith, A.,

137
Roblin, D., Silverberg, M., Tangpricha, V., Vupputuri, V., & Goodman, M.
(2020, October 17). Visual conformity with affirmed gender or “passing”: Its
distribution and association with depression and anxiety in a cohort of
transgender people. Journal of Sexual Medicine, 17(10), 2084–
2092. https://doi.org/10.1016/j.jsxm.2020.07.019Treharne, G. J., Blakey, A. G.,
Graham, K., Carrington, S. D., McLachlan, L. A., Withey-Rila, C., PearmanBeres,
L., & Anderson, L. (2021). Perspectives on expertise in teaching about
transgender healthcare: a focus group study with health professional programme
teaching staff and transgender community members. International Journal of
Transgender Health, 23(3), 334–354.
https://doi.org/10.1080/26895269.2020.1870189
Van Laar, C., Meeussen, L., Veldman, J., Van Grootel, S., Sterk, N., & Jacobs, C. (2019).
Coping with stigma in the workplace: understanding the role of threat regulation,
supportive factors, and potential hidden costs. Frontiers in Psychology, 1–21.
https://doi.org/10.3389/fpsyg.2019.01879
Vincent, B. (2019). Breaking down barriers and binaries in trans healthcare: the
validation of non-binary people. International Journal of
Transgenderism, 20(2/3), 132–137.
https://doi.org/10.1080/15532739.2018.1534075
Wagner, T. L., Kitzie, V. L., & Lookingbill, V. (2022). Transgender and nonbinary
individuals and ICT-driven information practices in response to transexclusionary
healthcare systems: a qualitative study. Journal of the American Medical

138
Informatics Association, 29(2), 239–248. https://doi.org/10.1093/jamia/ocab234
Wesp, L. M., Malcoe, L. H., Elliott, A., & Poteat, T. (2019). Intersectionality research for
transgender health justice: a theory-driven conceptual framework for structural
analysis of transgender health inequities. Transgender Health, 4(1), 287–296.
https://doi.org/10.1089/trgh.2019.0039
Westbrook, L., & Schlit, K. (2014). Transgender people, gender panics, and the
maintenance of the sex/gender/sexuality system. Gender & Society, 28(1), 32-57.
https://doi.org/10.1177/0891243213508008
Whipple, K. (2021). The SAGE Encyclopedia of Trans Studies. (Vols. 1-2). SAGE
Publications.https://dx.doi.org/10.4135/9781544393858
White, H., & Sabarwal, S. (2014). Quasi-experimental design and methods
(Methodological Briefs: Impact Evaluation 8). UNICEF Office of
Research.Wichinski, K. A. (2015). Providing culturally proficient care for
transgender. Nursing, 45(2), 58–63.
https://doi.org/10.1097/01.NURSE.0000456370.79660.f8
Willging, C., Gunderson, L., Shattuck, D., Sturm, R., Lawyer, A., & Crandall, C. (2019).
Structural competency in emergency medicine services for transgender and gender
non-conforming patients. Social Science & Medicine, 222, 67–75.
https://doi.org/10.1016/j.socscimed.2018.12.031
Witt, H., & Medina-Martinez, K. (2022). Transgender rights & the urgent need for social
work advocacy. Social Work in Public Health, 37(1), 28–32.
https://doi.org/10.1080/19371918.2021.1970685

139
Wootton, A. R. (2024). To reduce sexual minority health care disparities, advocate for
expanded health insurance coverage and LGBTQ+ rights. American Journal of
Public Health, 114(1), 12–14. https://doi.org/10.2105/AJPH.2023.307513
Abdou, C. M., Fingerhut, A. W., Jackson, J. S., & Wheaton, F. (2016). Healthcare
stereotype threat in older adults in the health and retirement study. American
Journal of Preventive Medicine, 50(2), 191–198.
https://doi.org/10.1016/j.amepre.2015.07.034
Adegoke, A.O. (2018). On the Effects of Nonlinearity Between Variables on the
Correlation Coefficient. [University of Regina].
Arayasirikul, S., & Wilson, E. C. (2019). Spilling the t on trans-misogyny and
microaggressions: An intersectional oppression and social process among trans
women. Journal of Homosexuality, 66(10), 1415–1438.
https://doi.org/10.1080/00918369.2018.1542203
Asamoah, M. K. (2014). Re-examination of the limitations associated with correlational
research. Journal of Educational Research and Reviews, 2(4), 45–52.
Baboolall, D., Greenberg, S., Obeid, M., & Zucker, J. (2022). Being transgender at work.
McKinsey Quarterly, 1, 1–18.
Blackwell, C. W., Diaz-Cruz, A., & Yan, X. (2020). Equality and quality: The relationship
between Magnet® status and healthcare organizational commitment to lesbian,
gay, bisexual, and transgender equality. Journal of Social Service
Research, 46(5), 705–712. https://doi.org/10.1080/01488376.2019.1645796

140
Blazucki, S. (2023). The Equal Rights Amendment and the Equality Act: Closing Gaps
Post-Bostock for Sexual Orientation and Gender Identity Minorities. University of
the District of Columbia Law Review, 26 (1), Article 4.
Boe, J. L., Ellis, E. M., Sharstrom, K. A., & Gale, J. E. (2020). Disrupting cisnormativity,
transnormativity, and transmisogyny in healthcare: Advancing trans inclusive
practices for medical family therapists. Journal of Feminist Family Therapy,
32(3/4), 157–175. https://doi.org/10.1080/08952833.2020.1848051
Boot-Haury, J. W. (2023). A preliminary study of intensive transgender-specific cultural
competency training: Implications for social workers and psychologists who work
with rural transgender clients. Journal of Gay & Lesbian Social Services, 1–27.
https://doi.org/10.1080/10538720.2023.2266399
Brothers, K., Rivera, S., Cadigan, R., Sharp, R., & Goldenberg, A. (2019). A Belmont
reboot: Building a normative foundation for human research in the 21st century.
Journal of Law, Medicine & Ethics, 47(1), 165-172.
https://doi.org/10.1177/1073110519840497
Burgess, D. J., Warren, J., Phelan, S., Dovidio, J., & van Ryn, M. (2010). Stereotype
threat and health disparities: What medical educators and future physicians need
to know. Journal of General Internal Medicine, 25 Suppl 2(Suppl 2), S169–S177.
https://doi.org/10.1007/s11606-009-1221-4
Cabacungan, A., Lee, J., Chaney, B., & Averett, P. (2019). Does gender minority
professional experience impact employment discrimination? Two résumé
experiments. Journal of Youth Development, 14(4), 267–284.

141
https://doi.org/10.5195/jyd.2019.829
Canvin, L., Twist, J., & Solomons, W. (2023). “I don’t want to say the wrong thing”:
Mental health professionals’ narratives of feeling inadequately skilled when
working with gender diverse adults. Psychology & Sexuality, 14(2), 337–350.
https://doi.org/10.1080/19419899.2022.2118070
Castañeda, E., & Smith, C. (2023). Conducting research with marginalized populations:
Methodological, ethical, and IRB considerations. Journal of Applied Social
Sciences (19367244), 17(1), 111–131.
https://doi.org/10.1177/19367244221141326
Casey, L. S., Reisner, S. L., Findling, M. G., Blendon, R. J., Benson, J. M., Sayde, J. M.,
& Miller, C. (2019). Discrimination in the United States: Experiences of lesbian,
gay, bisexual, transgender, and queer Americans. Health Services Research, 54,
1454–1466. https://doi.org/10.1111/1475-6773.13229
Chirkov, V., & Anderson, J. (2018). Statistical positivism versus critical scientific realism
A comparison of two paradigms for motivation research: Part 1 A philosophical
and empirical analysis of statistical positivism. Theory &
Psychology, 28(6), 712–736. https://doi.org/10.1177/0959354318804670
Creswell, J. W., & Creswell, J. D. (2018). Research design: Qualitative, quantitative, and
mixed methods approaches. (5th ed.). SAGE Publications, Inc.
Dahlen, S. (2020). De-sexing the medical record? An examination of sex versus gender
identity in the general medical council’s trans healthcare ethical advice. New
bioethics, 26(1), 38–52. https://doi.org/10.1080/20502877.2020.1720429

142
Davidson, S., & Halsall, J. (2016). Gender inequality: Nonbinary transgender people in
the workplace. Cogent Social Sciences, 2(1), N.PAG.
https://doi.org/10.1080/23311886.2016.1236511
Davidson, S. (2016, August 16). Gender inequality: Nonbinary transgender people in the
workplace. Cogent Social Sciences, Volume 2, Issue 1.
https://www.tandfonline.com/doi/full/10.1080/23311886.2016.1236511
DiPalma, L. M. (2021). Gender and sexual orientation in the workplace. Research
Starters: Sociology.
Dixon, J., & Dougherty, D. S. (2014). A language convergence/meaning divergence
analysis exploring how LGBTQ and single employees manage traditional family
expectations in the workplace. Journal of Applied Communication
Research, 42(1), 1–19. https://doi.org/10.1080/00909882.2013.847275
Doyle, D. M. (2022). Transgender identity: development, management and affirmation.
Current Opinion in Psychology, 48.
https://doi.org/10.1016/j.copsyc.2022.101467
Doyle, D. M., Begeny, C. T., Barreto, M., & Morton, T. A. (2021). Identity-related factors
protect well-being against stigma for transgender and gender nonconforming
people. Archives of Sexual Behavior, 50(7), 3191–3200.
https://doi.org/10.1007/s10508-021-02029-1
Elias, N. M. R. (2017). Constructing and implementing transgender policy for public
administration. Administration & Society, 49(1), 20–47.
https://doi.org/10.1177/0095399716684888

143
Enders, F. T., Golembiewski, E. H., Pacheco-Spann, L. M., Allyse, M., Mielke, M. M., &
Balls-Berry, J. E. (2021). Building a framework for inclusion in health services
research: Development of and pre-implementation faculty and staff attitudes
toward the Diversity, Equity, and Inclusion (DEI) plan at Mayo Clinic. Journal of
Clinical & Translational Science, 5(1), 1–10. https://doi.org/10.1017/cts.2020.575
Flynn, M. K., & Bhambhani, Y. (2021). Internalized transphobia, nondisclosure of gender
identity, and life satisfaction among transgender and non-binary adults:
The moderating roles of psychological flexibility and inflexibility. Journal of
Contextual Behavioral Science, 20, 194–201.
https://doi.org/10.1016/j.jcbs.2021.04.008
Frankfort-Nachmias, C., Leon-Guerrero, A., Davis, G. (2021). Social statistics for a
diverse society (9th ed.). SAGE Publications, Inc.
Freedman, D. A. (2005). Statistical Models: Theory and Practice. Cambridge University
Press.
Friesen, P., Kearns, L., Redman, B., & Caplan, A. L. (2017). Rethinking the Belmont
Report? American Journal of Bioethics, 17(7), 15–21.
https://doi.org/10.1080/15265161.2017.1329482
Galupo, M. P., & Resnick, C. A. (2016). Experiences of LGBT microaggressions in the
workplace: Implications for policy. In T. Köllen (Ed.), Sexual orientation and
transgender issues in organizations (pp. 271-287).
Springer. https://doi.org/10.1007/978-3-319-29623-4_16
Ghosh, B. (2022). State, citizenship and gender-variant communities in India. Citizenship
Studies, 26(2), 127–145. https://doi.org/10.1080/13621025.2021.2024147

144
Giffort, D. M., & Underman, K. (2016). The relationship between medical education and
trans health disparities: a call to research. Sociology Compass, 10(11), 999–1013.
https://doi.org/10.1111/soc4.12432
Goldbach, C., Knutson, D., & Kler, S. (2021). The SAGE Encyclopedia of Trans Studies
(Vols. 1–2). SAGE Publications, Inc. https://doi.org/10.4135/9781544393858
Goldenberg, T., Reisner, S. L., Harper, G. W., Gamarel, K. E., & Stephenson, R. (2020).
State policies and healthcare use among transgender people in the U.S. American
Journal of Preventive Medicine, 59(2), 247–259.
https://doi.org/10.1016/j.amepre.2020.01.030
Goszkowicz, K., & Davis, P. (2023). Reducing Adult transgender barriers to care in the
emergency department: strategies to improve policies and practices. Advanced
Emergency Nursing Journal, 45(1), 3–10.
https://doi.org/10.1097/TME.0000000000000446
Green, E. & Mauer, L. (2015). Glossary of transgender terms, The Teaching Transgender
Toolkit. Second Edition, 53-56.
Hasan, M. N. (2016). Positivism: to what extent does it aid our understanding of the
contemporary social world? Quality & Quantity, 50(1), 317–325.
https://doi.org/10.1007/s11135-014-0150-4
Hazra, A., & Gogtay, N. (2016). Biostatistics Series Module 6: Correlation and Linear
Regression. Indian Journal of Dermatology, 61(6), 593–601.
https://doi.org/10.4103/0019-5154.193662

145
Herman, J., Flores, A., & O’Neill, K. (2022, June). How many adults and youth identify
as transgender in the United States? UCLA School of Law Williams Institute.
https://williamsinstitute.law.ucla.edu/wp-content/uploads/Trans-Pop-Update-
Jun2022.pdf
Hossain, M., Atif, M., Ahmed, A., & Mia, L. (2020). Do LGBT workplace diversity
policies create value for firms? Journal of Business Ethics, 167(4), 775–791.
https://doi.org/10.1007/s10551-019-04158-z
Huffman, A. H., Mills, M. J., Howes, S. S., & Albritton, M. D. (2021). Workplace support
and affirming behaviors: moving toward a transgender, gender diverse, and non-
binary friendly workplace. International Journal of Transgender
Health, 22(3), 225–242. https://doi.org/10.1080/26895269.2020.1861575
Hughto, J. M. W., Gunn, H. A., Rood, B. A., & Pantalone, D. W. (2020). Social and
medical gender affirmation experiences are inversely associated with mental
health problems in a U.S. non-probability sample of transgender adults. archives
of sexual behavior, 49(7), 2635–2647. https://doi.org/10.1007/s10508-020-01655-
5
Human Rights Campaign Foundation. (2022). Health equality index: promoting equitable
and inclusive care for LGBTQ+ patients and their families. Washington, DC.
Johnson, A. H., Hillb, I., Beach-Ferrara, J., Rogers, B. A., & Bradford, A. (2020).
Common barriers to healthcare for transgender people in the U.S.
Southeast. International Journal of Transgender Health, 21(1), 70–78.
https://doi.org/10.1080/15532739.2019.1700203

146
Kanamori, Y., & Cornelius-White, J. H. D. (2016). Big changes, but are they big enough?
Healthcare professionals’ attitudes toward transgender persons. International
Journal of Transgenderism, 17(3/4), 165–175.
https://doi.org/10.1080/15532739.2016.1232628
Kattari, S. K., Bakko, M., Hecht, H. K., & Kattari, L. (2020). Correlations between
healthcare provider interactions and mental health among transgender and
nonbinary adults. SSM: Population Health, 10.
https://doi.org/10.1016/j.ssmph.2019.100525
Katz-Wise, S. L., Boskey, E. R., Godwin, E. G., Thomson, K., Post, J., & Gordon, A. R.
(2022). “We’re moving in the right direction. Still a long way to go”: Experiences
and perceptions of the climate for LGBTQ+ employees at a pediatric hospital.
Journal of Homosexuality, 69(13), 2286–2304.
https://doi.org/10.1080/00918369.2021.1938468
Khaikin, C. & Uttley, L. (2016) Growth of catholic hospitals and health systems: 2016
update of the miscarriage of medicine report. Merger Watch.
http://static1.1.sqspcdn.com/static/f/816571/27061007/1465224862580/MW_Upd
ate-2016-
MiscarrOfMedicinereport.pdf?token=rf3rsQaaCVCzLV9hKOIHuFcaWiU%3D.
King, W. M., & Gamarel, K. E. (2021). A scoping review examining social and legal
gender affirmation and health among transgender populations. Transgender
Health, 6(1), 5–22. https://doi.org/10.1089/trgh.2020.0025

147
Kleintop, L. K. (2019). When transgender employees come out: perceived support and
cultural change in the transition process. Journal of Business Diversity, 19(5), 55–
67. https://doi.org/10.33423/jbd.v19i5.2645
Koch, J. M., McLachlan, C., Victor, C. J., Westcott, J., & Yager, C. (2020). The cost of
being transgender: where socio-economic status, global health care systems, and gender
identity intersect. Psychology & Sexuality, 11(1–2), 103–119.
https://doi.org/10.1080/19419899.2019.1660705
Krueger, E. A., Divsalar, S., Luhur, W., Choi, S. K., & Meyer, I. H. (2020). TransPop -
U.S. Transgender Population Health Survey (Methodology and Technical Notes).
Los Angeles, CA: The Williams Institute. Retrieved from:
https://www.transpop.org/s/TransPop-Survey-Methods-v18-FINAL-copy.pdf
Lakens, D., & Caldwell, A. R. (2021). Simulation-based power analysis for factorial
analysis of variance designs. Advances in Methods and Practices in Psychological
Science. https://doi.org/10.1177/2515245920951503
Leppel, K. (2016). The labor force status of transgender men and women. International
Journal of Transgenderism, 17(3/4), 155–164.
https://doi.org/10.1080/15532739.2016.1236312
Leppel, K. (2021). Transgender men and women in 2015: employed, unemployed, or not
in the labor force. Journal of Homosexuality, 68(2), 203–229.
https://doi.org/10.1080/00918369.2019.1648081

148
Lerner, J. E., Martin, J. I., & Gorsky, G. S. (2021). More than an apple a day: factors
associated with avoidance of doctor visits among transgender, gender
nonconforming, and nonbinary people in the USA. Sexuality Research & Social
Policy: Journal of NSRC, 18(2), 409–426. https://doi.org/10.1007/s13178-020-
00469-3
Liu, M., Sandhu, Keuroghlian, A, (2022, July 28). Achieving the triple aim for sexual and
gender minorities. The New England Journal of Medicine, 2022; 387:294-297. http://doi/
10.1056/NEJMp2204569
McGregor, B., Belton, A., Henry, T. L., Wrenn, G., & Holden, K. B. (2019). Improving
behavioral health equity through cultural competence training of health care
providers. Ethnicity & Disease, 29, 359–364.
https://doi.org/10.18865/ed.29.S2.359
McNulty, Y., McPhail, R., Inversi, C., Dundon, T., & Nechanska, E. (2018). Employee
voice mechanisms for lesbian, gay, bisexual and transgender expatriation: the role
of Employee-Resource Groups (ERGs) and allies. International Journal of
Human Resource Management, 29(5), 829–856.
https://doi.org/10.1080/09585192.2017.1376221
Meyer, H. (2016). Dignity’s transgender bias case could signal more religious freedom
clashes. Modern Healthcare, 46(33), 10–11.
Meyer, I. (2021) TransPop, United States, 2016-2018. Interuniversity Consortium for
Political and Social Research. https://doi.org/10.3886/ICPSR37938.v1

149
Meyer, I. H., Wilson, B. D. M., & O'Neill, K. (2021). LGBTQ people in the US: Select
findings from the generations and TransPop studies. Williams Institute, UCLA
School of Law.
Mizock, L., Woodrum, T. D., Riley, J., Sotilleo, E. A., Yuen, N., & Ormerod, A.
J. (2017). Coping with transphobia in employment: strategies used by transgender
and gender-diverse people in the United States. International Journal of
Transgenderism, 18(3), 282–294.
https://doi.org/10.1080/15532739.2017.1304313
Nadal, K. L., Whitman, C. N., Davis, L. S., Erazo, T., & Davidoff, K. C. (2016).
Microaggressions toward lesbian, gay, bisexual, transgender, queer, and
genderqueer people: a review of the literature. Journal of Sex Research, 53(4/5),
488–508. https://doi.org/10.1080/00224499.2016.1142495
Newman, C. E., Prankumar, S. K., Cover, R., Rasmussen, M. L., Marshall, D., &
Aggleton, P. (2021). Inclusive health care for LGBTQ+ youth: support, belonging,
and inclusivity labour. Critical Public Health, 31(4), 441–450.
https://doi.org/10.1080/09581596.2020.1725443
Owens, B., Mills, S., Lewis, N., & Guta, A. (2022). Work-related stressors and mental
health among LGBTQ workers: Results from a cross-sectional survey. PLoS
ONE, 17(10), 1–14. https://doi.org/10.1371/journal.pone.0275771
Parr, N. J., & Howe, B. G. (2020). Factors associated with frequency of gender identity
non-affirmation microaggressions among transgender persons. Culture, Health &
Sexuality. https://doi.org/10.1080/13691058.2020.1755454

150
Perales, F., Ablaza, C., Tomaszewski, W., & Emsen-Hough, D. (2021). You, me, and
them: understanding employees’ use of trans-affirming language within the
workplace. Sexuality Research & Social Policy: A Journal of the NSRC.
https://doi.org/10.1007/s13178-021-00592-9
Perone, A. K. (2020). Protecting health care for transgender older adults amidst a
backlash of US federal policies. Journal of Gerontological Social Work, 63(8),
743–752. https://doi.org/10.1080/01634372.2020.1808139
Petchko, K. (2018). How to write about economics and public policy. Academic Press,
271-300. https://doi.org/10.1016/B978-0-12-813010-0.00014-4.
Piegza, M., & Główczyński, P. (2022). Minority stress and selected mental disorders in
people with gender dysphoria and gender incongruence – a narrative review.
Medycyna Pracy, 73(2), 163–172.
https://doi.org/10.13075/mp.5893.01198
Reisner, S. L., Gamarel, K. E., Mizock, L., White Hughto, J. M., Keuroghlian, A. S., &
Pachankis, J. E. (2016). Discriminatory experiences associated with posttraumatic
stress disorder symptoms among transgender adults. Journal of Counseling
Psychology, 63(5), 509–519. https://doi.org/10.1037/cou0000143
Reisner, S. L., & Hughto, J. M. W. (2019). Comparing the health of non-binary and
binary transgender adults in a statewide non-probability sample. PLoS
ONE, 14(8), 1–20. https://doi.org/10.1371/journal.pone.0221583
Reisner, S. L., Hughto, J. M. W., Dunham, E. E., Heflin, K. J., Begenyi, J. B. G., Coffey,
E. J., & Cahill, S. (2015). Legal protections in public accommodations settings: a

151
critical public health issue for transgender and gender-nonconforming people.
Milbank Quarterly, 93(3), 484–515. https://doi.org/10.1111/1468-
0009.12127
Reisner, S. L., Moore, C. S., Asquith, A., Pardee, D. J., & Mayer, K. H. (2020). Gender
non-affirmation from cisgender male partners: development and validation of a
brief stigma scale for HIV research with transgender men who have sex with men
(Trans MSM). AIDS & Behavior, 24(1), 331–343. https://doi.org/10.1007/s10461-
019-02749-5
Robinson, M. (2020). Two-spirit identity in a time of gender fluidity. Journal of
Homosexuality, 67(12), 1675–1690.
https://doi.org/10.1080/00918369.2019.1613853
Rood, B. A., Puckett, J. A., Reisner, S. L., Maroney, M. R., Berman, A. K., & Pantalone,
D. W. (2017). Identity concealment in transgender adults: A qualitative assessment
of minority stress and gender affirmation. American Journal of
Orthopsychiatry, 87(6), 704–713. https://doi.org/10.1037/ort0000303
Rosich, Gina R. (2020). Sexual citizenship theory and employment discrimination among
transgender-identified people. Societies, 10(1), 17.
https://doi.org/10.3390/soc10010017
Rouse, M., Jr., & Hamilton, E. (2021). Rethinking sex and the brain: how to create an
inclusive discourse in neuroscience. Mind, Brain, and Education, 15(2), 163–167. Rusow,
J. A., Hidalgo, M. A., Calvetti, S., Quint, M., Wu, S., Bray, B. C., & Kipke, M.
D. (2022). Health and service utilization among a sample of gender-diverse youth
of color: the TRUTH study. BMC Public Health, 22(1), 1–13.

152
https://doi.org/10.1186/s12889-022-14585-9
Saunders, R. K., Carr, D. C., & Burdette, A. M. (2023). Health care stereotype threat and
sexual and gender minority well-being. journal of health & social behavior, 1.
https://doi.org/10.1177/00221465231205549
Sawyer, K., & Thoroughgood, C. (2017). Gender non-conformity and the modern
workplace: new frontiers in understanding and promoting gender identity
expression at work. Organizational Dynamics, 46(1), 1–8.
https://doi.org/10.1016/j.orgdyn.2017.01.001
Scott, D., Pereira, N. M., Harrison, S. E., Zarwell, M., Sanasi-Bhola, K., & Poteat, T.
(2021). “In the Bible Belt:” The role of religion in HIV care and prevention for
transgender people in the United States south. Health & Place, 70, N.PAG.
https://doi.org/10.1016/j.healthplace.2021.1
Seelman, K. L., & Poteat, T. (2020). Strategies used by transmasculine and non-binary
adults assigned female at birth to resist transgender stigma in healthcare.
International Journal of Transgender Health, 21(3), 350–365.
https://doi.org/10.1080/26895269.2020.1781017
Serano, J. (2021). The SAGE Encyclopedia of Trans Studies (Vols. 1-2). SAGE
Publications. https://dx.doi.org/10.4135/9781544393858
Sevelius J. (2013). Gender affirmation: a framework for conceptualizing risk behavior
among transgender women of color. Sex Roles. 68(11–12):675–689.
https://doi.org/10.1007/s11199-012-0216-5

153
Sherman, B., Kelly, R., & Payne-Foster, P. (2021). Integrating workforce health into
employer diversity, equity, and inclusion efforts. American Journal of Health
Promotion, 35(5), 609–612. https://doi.org/10.1177/0890117120983288
Siad, F. & Rabi, D. (2021). Harassment in the field of medicine: cultural barriers to
psychological safety. CJC Open, 3(12), S174–S179.
https://doi.org/10.1016/j.cjco.2021.08.018
Smart, B. D., Mann-Jackson, L., Alonzo, J., Tanner, A. E., Garcia, M., Refugio Aviles,
L., & Rhodes, S. D. (2022). Transgender women of color in the US South: A
qualitative study of social determinants of health and healthcare perspectives.
International Journal of Transgender Health, 23(1–2), 164–177.
https://doi.org/10.1080/26895269.2020.1848691
Stewart, C. (2020). The future is queer kids: Queering the homonormative temporalities
of same-sex marriage. Politics, 40(3), 265–280.
https://doi.org/10.1177/0263395719872595
Stroumsa, D., Shires, D. A., Richardson, C. R., Jaffee, K. D., & Woodford, M. R. (2019).
Transphobia rather than education predicts provider knowledge of transgender
health care. Medical Education, 53(4), 398–407.
https://doi.org/10.1111/medu.13796
Szemanski, A. (2020). When trans rights are disability rights: the promises and perils of
seeking gender dysphoria coverage under the Americans with disabilities act.
Harvard Journal of Law & Gender, 43(1), 137–168.
Taber, J. M., Howell, J. L., Emanuel, A. S., Klein, W. M. P., Ferrer, R. A., & Harris, P.
R. (2016). Associations of spontaneous self-affirmation with health care

154
experiences and health information seeking in a national survey of US adults.
Psychology & Health, 31(3), 292–309.
https://doi.org/10.1080/08870446.2015.1085986
Thorne, N., Yip, A. K.-T., Bouman, W. P., Marshall, E., & Arcelus, J. (2019). The
terminology of identities between, outside and beyond the gender binary – a
systematic review. International Journal of Transgenderism, 20(2/3), 138–154.
https://doi.org/10.1080/15532739.2019.1640654
Thoroughgood, C. N., Sawyer, K. B., & Webster, J. R. (2020). Creating a trans-inclusive
workplace: how to make transgender employees feel valued at work. Harvard
Business Review, 98(2), 114.
Thoroughgood, C. N., Sawyer, K. B., & Webster, J. R. (2017). What lies beneath: how
paranoid cognition explains the relations between transgender employees'
perceptions of discrimination at work and their job attitudes and well-being.
Journal of Vocational Behavior, 103, 99–112.
https://doi.org/10.1016/j.jvb.2017.07.009
Thorpe, S., Tanner, A. E., & Hargons, C. N. (2022). Sexual identity factors and minority
stressors associated with healthcare stereotype threat and access to care among
Black sexual minority women. Journal of Gay & Lesbian Social Services, 1–21.
https://doi.org/10.1080/10538720.2022.2056398
To, M., Zhang, Q., Bradlyn, A., Getahun, D., Giammattei, S., Nash, R., Owen-Smith, A.,
Roblin, D., Silverberg, M., Tangpricha, V., Vupputuri, V., & Goodman, M.

155
(2020, October 17). Visual conformity with affirmed gender or “passing”: Its
distribution and association with depression and anxiety in a cohort of
transgender people. Journal of Sexual Medicine, 17(10), 2084–
2092. https://doi.org/10.1016/j.jsxm.2020.07.019Treharne, G. J., Blakey, A. G.,
Graham, K., Carrington, S. D., McLachlan, L. A., Withey-Rila, C., PearmanBeres,
L., & Anderson, L. (2021). Perspectives on expertise in teaching about
transgender healthcare: a focus group study with health professional programme
teaching staff and transgender community members. International Journal of
Transgender Health, 23(3), 334–354.
https://doi.org/10.1080/26895269.2020.1870189
Van Laar, C., Meeussen, L., Veldman, J., Van Grootel, S., Sterk, N., & Jacobs, C. (2019).
Coping with stigma in the workplace: understanding the role of threat regulation,
supportive factors, and potential hidden costs. Frontiers in Psychology, 1–21.
https://doi.org/10.3389/fpsyg.2019.01879
Vincent, B. (2019). Breaking down barriers and binaries in trans healthcare: the
validation of non-binary people. International Journal of
Transgenderism, 20(2/3), 132–137.
https://doi.org/10.1080/15532739.2018.1534075
Wagner, T. L., Kitzie, V. L., & Lookingbill, V. (2022). Transgender and nonbinary
individuals and ICT-driven information practices in response to transexclusionary
healthcare systems: a qualitative study. Journal of the American Medical
Informatics Association, 29(2), 239–248. https://doi.org/10.1093/jamia/ocab234

156
Wesp, L. M., Malcoe, L. H., Elliott, A., & Poteat, T. (2019). Intersectionality research for
transgender health justice: a theory-driven conceptual framework for structural
analysis of transgender health inequities. Transgender Health, 4(1), 287–296.
https://doi.org/10.1089/trgh.2019.0039
Westbrook, L., & Schlit, K. (2014). Transgender people, gender panics, and the
maintenance of the sex/gender/sexuality system. Gender & Society, 28(1), 32-57.
https://doi.org/10.1177/0891243213508008
Whipple, K. (2021). The SAGE Encyclopedia of Trans Studies. (Vols. 1-2). SAGE
Publications.https://dx.doi.org/10.4135/9781544393858
White, H., & Sabarwal, S. (2014). Quasi-experimental design and methods
(Methodological Briefs: Impact Evaluation 8). UNICEF Office of
Research.Wichinski, K. A. (2015). Providing culturally proficient care for
transgender. Nursing, 45(2), 58–63.
https://doi.org/10.1097/01.NURSE.0000456370.79660.f8
Willging, C., Gunderson, L., Shattuck, D., Sturm, R., Lawyer, A., & Crandall, C. (2019).
Structural competency in emergency medicine services for transgender and gender
non-conforming patients. Social Science & Medicine, 222, 67–75.
https://doi.org/10.1016/j.socscimed.2018.12.031
Witt, H., & Medina-Martinez, K. (2022). Transgender rights & the urgent need for social
work advocacy. Social Work in Public Health, 37(1), 28–32.
https://doi.org/10.1080/19371918.2021.1970685

157
Wootton, A. R. (2024). To reduce sexual minority health care disparities, advocate for
expanded health insurance coverage and LGBTQ+ rights. American Journal of
Public Health, 114(1), 12–14. https://doi.org/10.2105/AJPH.2023.307513
Abdou, C. M., Fingerhut, A. W., Jackson, J. S., & Wheaton, F. (2016). Healthcare
stereotype threat in older adults in the health and retirement study. American
Journal of Preventive Medicine, 50(2), 191–198.
https://doi.org/10.1016/j.amepre.2015.07.034
Adegoke, A.O. (2018). On the Effects of Nonlinearity Between Variables on the
Correlation Coefficient. [University of Regina].
Arayasirikul, S., & Wilson, E. C. (2019). Spilling the t on trans-misogyny and
microaggressions: An intersectional oppression and social process among trans
women. Journal of Homosexuality, 66(10), 1415–1438.
https://doi.org/10.1080/00918369.2018.1542203
Asamoah, M. K. (2014). Re-examination of the limitations associated with correlational
research. Journal of Educational Research and Reviews, 2(4), 45–52.
Baboolall, D., Greenberg, S., Obeid, M., & Zucker, J. (2022). Being transgender at work.
McKinsey Quarterly, 1, 1–18.
Blackwell, C. W., Diaz-Cruz, A., & Yan, X. (2020). Equality and quality: The relationship
between Magnet® status and healthcare organizational commitment to lesbian,
gay, bisexual, and transgender equality. Journal of Social Service
Research, 46(5), 705–712. https://doi.org/10.1080/01488376.2019.1645796

158
Blazucki, S. (2023). The Equal Rights Amendment and the Equality Act: Closing Gaps
Post-Bostock for Sexual Orientation and Gender Identity Minorities. University of
the District of Columbia Law Review, 26 (1), Article 4.
Boe, J. L., Ellis, E. M., Sharstrom, K. A., & Gale, J. E. (2020). Disrupting cisnormativity,
transnormativity, and transmisogyny in healthcare: Advancing trans inclusive
practices for medical family therapists. Journal of Feminist Family Therapy,
32(3/4), 157–175. https://doi.org/10.1080/08952833.2020.1848051
Boot-Haury, J. W. (2023). A preliminary study of intensive transgender-specific cultural
competency training: Implications for social workers and psychologists who work
with rural transgender clients. Journal of Gay & Lesbian Social Services, 1–27.
https://doi.org/10.1080/10538720.2023.2266399
Brothers, K., Rivera, S., Cadigan, R., Sharp, R., & Goldenberg, A. (2019). A Belmont
reboot: Building a normative foundation for human research in the 21st century.
Journal of Law, Medicine & Ethics, 47(1), 165-172.
https://doi.org/10.1177/1073110519840497
Burgess, D. J., Warren, J., Phelan, S., Dovidio, J., & van Ryn, M. (2010). Stereotype
threat and health disparities: What medical educators and future physicians need
to know. Journal of General Internal Medicine, 25 Suppl 2(Suppl 2), S169–S177.
https://doi.org/10.1007/s11606-009-1221-4
Cabacungan, A., Lee, J., Chaney, B., & Averett, P. (2019). Does gender minority
professional experience impact employment discrimination? Two résumé
experiments. Journal of Youth Development, 14(4), 267–284.

159
https://doi.org/10.5195/jyd.2019.829
Canvin, L., Twist, J., & Solomons, W. (2023). “I don’t want to say the wrong thing”:
Mental health professionals’ narratives of feeling inadequately skilled when
working with gender diverse adults. Psychology & Sexuality, 14(2), 337–350.
https://doi.org/10.1080/19419899.2022.2118070
Castañeda, E., & Smith, C. (2023). Conducting research with marginalized populations:
Methodological, ethical, and IRB considerations. Journal of Applied Social
Sciences (19367244), 17(1), 111–131.
https://doi.org/10.1177/19367244221141326
Casey, L. S., Reisner, S. L., Findling, M. G., Blendon, R. J., Benson, J. M., Sayde, J. M.,
& Miller, C. (2019). Discrimination in the United States: Experiences of lesbian,
gay, bisexual, transgender, and queer Americans. Health Services Research, 54,
1454–1466. https://doi.org/10.1111/1475-6773.13229
Chirkov, V., & Anderson, J. (2018). Statistical positivism versus critical scientific realism
A comparison of two paradigms for motivation research: Part 1 A philosophical
and empirical analysis of statistical positivism. Theory &
Psychology, 28(6), 712–736. https://doi.org/10.1177/0959354318804670
Creswell, J. W., & Creswell, J. D. (2018). Research design: Qualitative, quantitative, and
mixed methods approaches. (5th ed.). SAGE Publications, Inc.
Dahlen, S. (2020). De-sexing the medical record? An examination of sex versus gender
identity in the general medical council’s trans healthcare ethical advice. New
bioethics, 26(1), 38–52. https://doi.org/10.1080/20502877.2020.1720429

160
Davidson, S., & Halsall, J. (2016). Gender inequality: Nonbinary transgender people in
the workplace. Cogent Social Sciences, 2(1), N.PAG.
https://doi.org/10.1080/23311886.2016.1236511
Davidson, S. (2016, August 16). Gender inequality: Nonbinary transgender people in the
workplace. Cogent Social Sciences, Volume 2, Issue 1.
https://www.tandfonline.com/doi/full/10.1080/23311886.2016.1236511
DiPalma, L. M. (2021). Gender and sexual orientation in the workplace. Research
Starters: Sociology.
Dixon, J., & Dougherty, D. S. (2014). A language convergence/meaning divergence
analysis exploring how LGBTQ and single employees manage traditional family
expectations in the workplace. Journal of Applied Communication
Research, 42(1), 1–19. https://doi.org/10.1080/00909882.2013.847275
Doyle, D. M. (2022). Transgender identity: development, management and affirmation.
Current Opinion in Psychology, 48.
https://doi.org/10.1016/j.copsyc.2022.101467
Doyle, D. M., Begeny, C. T., Barreto, M., & Morton, T. A. (2021). Identity-related factors
protect well-being against stigma for transgender and gender nonconforming
people. Archives of Sexual Behavior, 50(7), 3191–3200.
https://doi.org/10.1007/s10508-021-02029-1
Elias, N. M. R. (2017). Constructing and implementing transgender policy for public
administration. Administration & Society, 49(1), 20–47.
https://doi.org/10.1177/0095399716684888

161
Enders, F. T., Golembiewski, E. H., Pacheco-Spann, L. M., Allyse, M., Mielke, M. M., &
Balls-Berry, J. E. (2021). Building a framework for inclusion in health services
research: Development of and pre-implementation faculty and staff attitudes
toward the Diversity, Equity, and Inclusion (DEI) plan at Mayo Clinic. Journal of
Clinical & Translational Science, 5(1), 1–10. https://doi.org/10.1017/cts.2020.575
Flynn, M. K., & Bhambhani, Y. (2021). Internalized transphobia, nondisclosure of gender
identity, and life satisfaction among transgender and non-binary adults:
The moderating roles of psychological flexibility and inflexibility. Journal of
Contextual Behavioral Science, 20, 194–201.
https://doi.org/10.1016/j.jcbs.2021.04.008
Frankfort-Nachmias, C., Leon-Guerrero, A., Davis, G. (2021). Social statistics for a
diverse society (9th ed.). SAGE Publications, Inc.
Freedman, D. A. (2005). Statistical Models: Theory and Practice. Cambridge University
Press.
Friesen, P., Kearns, L., Redman, B., & Caplan, A. L. (2017). Rethinking the Belmont
Report? American Journal of Bioethics, 17(7), 15–21.
https://doi.org/10.1080/15265161.2017.1329482
Galupo, M. P., & Resnick, C. A. (2016). Experiences of LGBT microaggressions in the
workplace: Implications for policy. In T. Köllen (Ed.), Sexual orientation and
transgender issues in organizations (pp. 271-287).
Springer. https://doi.org/10.1007/978-3-319-29623-4_16
Ghosh, B. (2022). State, citizenship and gender-variant communities in India. Citizenship
Studies, 26(2), 127–145. https://doi.org/10.1080/13621025.2021.2024147

162
Giffort, D. M., & Underman, K. (2016). The relationship between medical education and
trans health disparities: a call to research. Sociology Compass, 10(11), 999–1013.
https://doi.org/10.1111/soc4.12432
Goldbach, C., Knutson, D., & Kler, S. (2021). The SAGE Encyclopedia of Trans Studies
(Vols. 1–2). SAGE Publications, Inc. https://doi.org/10.4135/9781544393858
Goldenberg, T., Reisner, S. L., Harper, G. W., Gamarel, K. E., & Stephenson, R. (2020).
State policies and healthcare use among transgender people in the U.S. American
Journal of Preventive Medicine, 59(2), 247–259.
https://doi.org/10.1016/j.amepre.2020.01.030
Goszkowicz, K., & Davis, P. (2023). Reducing Adult transgender barriers to care in the
emergency department: strategies to improve policies and practices. Advanced
Emergency Nursing Journal, 45(1), 3–10.
https://doi.org/10.1097/TME.0000000000000446
Green, E. & Mauer, L. (2015). Glossary of transgender terms, The Teaching Transgender
Toolkit. Second Edition, 53-56.
Hasan, M. N. (2016). Positivism: to what extent does it aid our understanding of the
contemporary social world? Quality & Quantity, 50(1), 317–325.
https://doi.org/10.1007/s11135-014-0150-4
Hazra, A., & Gogtay, N. (2016). Biostatistics Series Module 6: Correlation and Linear
Regression. Indian Journal of Dermatology, 61(6), 593–601.
https://doi.org/10.4103/0019-5154.193662

163
Herman, J., Flores, A., & O’Neill, K. (2022, June). How many adults and youth identify
as transgender in the United States? UCLA School of Law Williams Institute.
https://williamsinstitute.law.ucla.edu/wp-content/uploads/Trans-Pop-Update-
Jun2022.pdf
Hossain, M., Atif, M., Ahmed, A., & Mia, L. (2020). Do LGBT workplace diversity
policies create value for firms? Journal of Business Ethics, 167(4), 775–791.
https://doi.org/10.1007/s10551-019-04158-z
Huffman, A. H., Mills, M. J., Howes, S. S., & Albritton, M. D. (2021). Workplace support
and affirming behaviors: moving toward a transgender, gender diverse, and non-
binary friendly workplace. International Journal of Transgender
Health, 22(3), 225–242. https://doi.org/10.1080/26895269.2020.1861575
Hughto, J. M. W., Gunn, H. A., Rood, B. A., & Pantalone, D. W. (2020). Social and
medical gender affirmation experiences are inversely associated with mental
health problems in a U.S. non-probability sample of transgender adults. archives
of sexual behavior, 49(7), 2635–2647. https://doi.org/10.1007/s10508-020-01655-
5
Human Rights Campaign Foundation. (2022). Health equality index: promoting equitable
and inclusive care for LGBTQ+ patients and their families. Washington, DC.
Johnson, A. H., Hillb, I., Beach-Ferrara, J., Rogers, B. A., & Bradford, A. (2020).
Common barriers to healthcare for transgender people in the U.S.
Southeast. International Journal of Transgender Health, 21(1), 70–78.
https://doi.org/10.1080/15532739.2019.1700203

164
Kanamori, Y., & Cornelius-White, J. H. D. (2016). Big changes, but are they big enough?
Healthcare professionals’ attitudes toward transgender persons. International
Journal of Transgenderism, 17(3/4), 165–175.
https://doi.org/10.1080/15532739.2016.1232628
Kattari, S. K., Bakko, M., Hecht, H. K., & Kattari, L. (2020). Correlations between
healthcare provider interactions and mental health among transgender and
nonbinary adults. SSM: Population Health, 10.
https://doi.org/10.1016/j.ssmph.2019.100525
Katz-Wise, S. L., Boskey, E. R., Godwin, E. G., Thomson, K., Post, J., & Gordon, A. R.
(2022). “We’re moving in the right direction. Still a long way to go”: Experiences
and perceptions of the climate for LGBTQ+ employees at a pediatric hospital.
Journal of Homosexuality, 69(13), 2286–2304.
https://doi.org/10.1080/00918369.2021.1938468
Khaikin, C. & Uttley, L. (2016) Growth of catholic hospitals and health systems: 2016
update of the miscarriage of medicine report. Merger Watch.
http://static1.1.sqspcdn.com/static/f/816571/27061007/1465224862580/MW_Upd
ate-2016-
MiscarrOfMedicinereport.pdf?token=rf3rsQaaCVCzLV9hKOIHuFcaWiU%3D.
King, W. M., & Gamarel, K. E. (2021). A scoping review examining social and legal
gender affirmation and health among transgender populations. Transgender
Health, 6(1), 5–22. https://doi.org/10.1089/trgh.2020.0025

165
Kleintop, L. K. (2019). When transgender employees come out: perceived support and
cultural change in the transition process. Journal of Business Diversity, 19(5), 55–
67. https://doi.org/10.33423/jbd.v19i5.2645
Koch, J. M., McLachlan, C., Victor, C. J., Westcott, J., & Yager, C. (2020). The cost of
being transgender: where socio-economic status, global health care systems, and gender
identity intersect. Psychology & Sexuality, 11(1–2), 103–119.
https://doi.org/10.1080/19419899.2019.1660705
Krueger, E. A., Divsalar, S., Luhur, W., Choi, S. K., & Meyer, I. H. (2020). TransPop -
U.S. Transgender Population Health Survey (Methodology and Technical Notes).
Los Angeles, CA: The Williams Institute. Retrieved from:
https://www.transpop.org/s/TransPop-Survey-Methods-v18-FINAL-copy.pdf
Lakens, D., & Caldwell, A. R. (2021). Simulation-based power analysis for factorial
analysis of variance designs. Advances in Methods and Practices in Psychological
Science. https://doi.org/10.1177/2515245920951503
Leppel, K. (2016). The labor force status of transgender men and women. International
Journal of Transgenderism, 17(3/4), 155–164.
https://doi.org/10.1080/15532739.2016.1236312
Leppel, K. (2021). Transgender men and women in 2015: employed, unemployed, or not
in the labor force. Journal of Homosexuality, 68(2), 203–229.
https://doi.org/10.1080/00918369.2019.1648081

166
Lerner, J. E., Martin, J. I., & Gorsky, G. S. (2021). More than an apple a day: factors
associated with avoidance of doctor visits among transgender, gender
nonconforming, and nonbinary people in the USA. Sexuality Research & Social
Policy: Journal of NSRC, 18(2), 409–426. https://doi.org/10.1007/s13178-020-
00469-3
Liu, M., Sandhu, Keuroghlian, A, (2022, July 28). Achieving the triple aim for sexual and
gender minorities. The New England Journal of Medicine, 2022; 387:294-297. http://doi/
10.1056/NEJMp2204569
McGregor, B., Belton, A., Henry, T. L., Wrenn, G., & Holden, K. B. (2019). Improving
behavioral health equity through cultural competence training of health care
providers. Ethnicity & Disease, 29, 359–364.
https://doi.org/10.18865/ed.29.S2.359
McNulty, Y., McPhail, R., Inversi, C., Dundon, T., & Nechanska, E. (2018). Employee
voice mechanisms for lesbian, gay, bisexual and transgender expatriation: the role
of Employee-Resource Groups (ERGs) and allies. International Journal of
Human Resource Management, 29(5), 829–856.
https://doi.org/10.1080/09585192.2017.1376221
Meyer, H. (2016). Dignity’s transgender bias case could signal more religious freedom
clashes. Modern Healthcare, 46(33), 10–11.
Meyer, I. (2021) TransPop, United States, 2016-2018. Interuniversity Consortium for
Political and Social Research. https://doi.org/10.3886/ICPSR37938.v1

167
Meyer, I. H., Wilson, B. D. M., & O'Neill, K. (2021). LGBTQ people in the US: Select
findings from the generations and TransPop studies. Williams Institute, UCLA
School of Law.
Mizock, L., Woodrum, T. D., Riley, J., Sotilleo, E. A., Yuen, N., & Ormerod, A.
J. (2017). Coping with transphobia in employment: strategies used by transgender
and gender-diverse people in the United States. International Journal of
Transgenderism, 18(3), 282–294.
https://doi.org/10.1080/15532739.2017.1304313
Nadal, K. L., Whitman, C. N., Davis, L. S., Erazo, T., & Davidoff, K. C. (2016).
Microaggressions toward lesbian, gay, bisexual, transgender, queer, and
genderqueer people: a review of the literature. Journal of Sex Research, 53(4/5),
488–508. https://doi.org/10.1080/00224499.2016.1142495
Newman, C. E., Prankumar, S. K., Cover, R., Rasmussen, M. L., Marshall, D., &
Aggleton, P. (2021). Inclusive health care for LGBTQ+ youth: support, belonging,
and inclusivity labour. Critical Public Health, 31(4), 441–450.
https://doi.org/10.1080/09581596.2020.1725443
Owens, B., Mills, S., Lewis, N., & Guta, A. (2022). Work-related stressors and mental
health among LGBTQ workers: Results from a cross-sectional survey. PLoS
ONE, 17(10), 1–14. https://doi.org/10.1371/journal.pone.0275771
Parr, N. J., & Howe, B. G. (2020). Factors associated with frequency of gender identity
non-affirmation microaggressions among transgender persons. Culture, Health &
Sexuality. https://doi.org/10.1080/13691058.2020.1755454

168
Perales, F., Ablaza, C., Tomaszewski, W., & Emsen-Hough, D. (2021). You, me, and
them: understanding employees’ use of trans-affirming language within the
workplace. Sexuality Research & Social Policy: A Journal of the NSRC.
https://doi.org/10.1007/s13178-021-00592-9
Perone, A. K. (2020). Protecting health care for transgender older adults amidst a
backlash of US federal policies. Journal of Gerontological Social Work, 63(8),
743–752. https://doi.org/10.1080/01634372.2020.1808139
Petchko, K. (2018). How to write about economics and public policy. Academic Press,
271-300. https://doi.org/10.1016/B978-0-12-813010-0.00014-4.
Piegza, M., & Główczyński, P. (2022). Minority stress and selected mental disorders in
people with gender dysphoria and gender incongruence – a narrative review.
Medycyna Pracy, 73(2), 163–172.
https://doi.org/10.13075/mp.5893.01198
Reisner, S. L., Gamarel, K. E., Mizock, L., White Hughto, J. M., Keuroghlian, A. S., &
Pachankis, J. E. (2016). Discriminatory experiences associated with posttraumatic
stress disorder symptoms among transgender adults. Journal of Counseling
Psychology, 63(5), 509–519. https://doi.org/10.1037/cou0000143
Reisner, S. L., & Hughto, J. M. W. (2019). Comparing the health of non-binary and
binary transgender adults in a statewide non-probability sample. PLoS
ONE, 14(8), 1–20. https://doi.org/10.1371/journal.pone.0221583
Reisner, S. L., Hughto, J. M. W., Dunham, E. E., Heflin, K. J., Begenyi, J. B. G., Coffey,
E. J., & Cahill, S. (2015). Legal protections in public accommodations settings: a

169
critical public health issue for transgender and gender-nonconforming people.
Milbank Quarterly, 93(3), 484–515. https://doi.org/10.1111/1468-
0009.12127
Reisner, S. L., Moore, C. S., Asquith, A., Pardee, D. J., & Mayer, K. H. (2020). Gender
non-affirmation from cisgender male partners: development and validation of a
brief stigma scale for HIV research with transgender men who have sex with men
(Trans MSM). AIDS & Behavior, 24(1), 331–343. https://doi.org/10.1007/s10461-
019-02749-5
Robinson, M. (2020). Two-spirit identity in a time of gender fluidity. Journal of
Homosexuality, 67(12), 1675–1690.
https://doi.org/10.1080/00918369.2019.1613853
Rood, B. A., Puckett, J. A., Reisner, S. L., Maroney, M. R., Berman, A. K., & Pantalone,
D. W. (2017). Identity concealment in transgender adults: A qualitative assessment
of minority stress and gender affirmation. American Journal of
Orthopsychiatry, 87(6), 704–713. https://doi.org/10.1037/ort0000303
Rosich, Gina R. (2020). Sexual citizenship theory and employment discrimination among
transgender-identified people. Societies, 10(1), 17.
https://doi.org/10.3390/soc10010017
Rouse, M., Jr., & Hamilton, E. (2021). Rethinking sex and the brain: how to create an
inclusive discourse in neuroscience. Mind, Brain, and Education, 15(2), 163–167. Rusow,
J. A., Hidalgo, M. A., Calvetti, S., Quint, M., Wu, S., Bray, B. C., & Kipke, M.
D. (2022). Health and service utilization among a sample of gender-diverse youth
of color: the TRUTH study. BMC Public Health, 22(1), 1–13.

170
https://doi.org/10.1186/s12889-022-14585-9
Saunders, R. K., Carr, D. C., & Burdette, A. M. (2023). Health care stereotype threat and
sexual and gender minority well-being. journal of health & social behavior, 1.
https://doi.org/10.1177/00221465231205549
Sawyer, K., & Thoroughgood, C. (2017). Gender non-conformity and the modern
workplace: new frontiers in understanding and promoting gender identity
expression at work. Organizational Dynamics, 46(1), 1–8.
https://doi.org/10.1016/j.orgdyn.2017.01.001
Scott, D., Pereira, N. M., Harrison, S. E., Zarwell, M., Sanasi-Bhola, K., & Poteat, T.
(2021). “In the Bible Belt:” The role of religion in HIV care and prevention for
transgender people in the United States south. Health & Place, 70, N.PAG.
https://doi.org/10.1016/j.healthplace.2021.1
Seelman, K. L., & Poteat, T. (2020). Strategies used by transmasculine and non-binary
adults assigned female at birth to resist transgender stigma in healthcare.
International Journal of Transgender Health, 21(3), 350–365.
https://doi.org/10.1080/26895269.2020.1781017
Serano, J. (2021). The SAGE Encyclopedia of Trans Studies (Vols. 1-2). SAGE
Publications. https://dx.doi.org/10.4135/9781544393858
Sevelius J. (2013). Gender affirmation: a framework for conceptualizing risk behavior
among transgender women of color. Sex Roles. 68(11–12):675–689.
https://doi.org/10.1007/s11199-012-0216-5

171
Sherman, B., Kelly, R., & Payne-Foster, P. (2021). Integrating workforce health into
employer diversity, equity, and inclusion efforts. American Journal of Health
Promotion, 35(5), 609–612. https://doi.org/10.1177/0890117120983288
Siad, F. & Rabi, D. (2021). Harassment in the field of medicine: cultural barriers to
psychological safety. CJC Open, 3(12), S174–S179.
https://doi.org/10.1016/j.cjco.2021.08.018
Smart, B. D., Mann-Jackson, L., Alonzo, J., Tanner, A. E., Garcia, M., Refugio Aviles,
L., & Rhodes, S. D. (2022). Transgender women of color in the US South: A
qualitative study of social determinants of health and healthcare perspectives.
International Journal of Transgender Health, 23(1–2), 164–177.
https://doi.org/10.1080/26895269.2020.1848691
Stewart, C. (2020). The future is queer kids: Queering the homonormative temporalities
of same-sex marriage. Politics, 40(3), 265–280.
https://doi.org/10.1177/0263395719872595
Stroumsa, D., Shires, D. A., Richardson, C. R., Jaffee, K. D., & Woodford, M. R. (2019).
Transphobia rather than education predicts provider knowledge of transgender
health care. Medical Education, 53(4), 398–407.
https://doi.org/10.1111/medu.13796
Szemanski, A. (2020). When trans rights are disability rights: the promises and perils of
seeking gender dysphoria coverage under the Americans with disabilities act.
Harvard Journal of Law & Gender, 43(1), 137–168.
Taber, J. M., Howell, J. L., Emanuel, A. S., Klein, W. M. P., Ferrer, R. A., & Harris, P.
R. (2016). Associations of spontaneous self-affirmation with health care

172
experiences and health information seeking in a national survey of US adults.
Psychology & Health, 31(3), 292–309.
https://doi.org/10.1080/08870446.2015.1085986
Thorne, N., Yip, A. K.-T., Bouman, W. P., Marshall, E., & Arcelus, J. (2019). The
terminology of identities between, outside and beyond the gender binary – a
systematic review. International Journal of Transgenderism, 20(2/3), 138–154.
https://doi.org/10.1080/15532739.2019.1640654
Thoroughgood, C. N., Sawyer, K. B., & Webster, J. R. (2020). Creating a trans-inclusive
workplace: how to make transgender employees feel valued at work. Harvard
Business Review, 98(2), 114.
Thoroughgood, C. N., Sawyer, K. B., & Webster, J. R. (2017). What lies beneath: how
paranoid cognition explains the relations between transgender employees'
perceptions of discrimination at work and their job attitudes and well-being.
Journal of Vocational Behavior, 103, 99–112.
https://doi.org/10.1016/j.jvb.2017.07.009
Thorpe, S., Tanner, A. E., & Hargons, C. N. (2022). Sexual identity factors and minority
stressors associated with healthcare stereotype threat and access to care among
Black sexual minority women. Journal of Gay & Lesbian Social Services, 1–21.
https://doi.org/10.1080/10538720.2022.2056398
To, M., Zhang, Q., Bradlyn, A., Getahun, D., Giammattei, S., Nash, R., Owen-Smith, A.,
Roblin, D., Silverberg, M., Tangpricha, V., Vupputuri, V., & Goodman, M.

173
(2020, October 17). Visual conformity with affirmed gender or “passing”: Its
distribution and association with depression and anxiety in a cohort of
transgender people. Journal of Sexual Medicine, 17(10), 2084–
2092. https://doi.org/10.1016/j.jsxm.2020.07.019Treharne, G. J., Blakey, A. G.,
Graham, K., Carrington, S. D., McLachlan, L. A., Withey-Rila, C., PearmanBeres,
L., & Anderson, L. (2021). Perspectives on expertise in teaching about
transgender healthcare: a focus group study with health professional programme
teaching staff and transgender community members. International Journal of
Transgender Health, 23(3), 334–354.
https://doi.org/10.1080/26895269.2020.1870189
Van Laar, C., Meeussen, L., Veldman, J., Van Grootel, S., Sterk, N., & Jacobs, C. (2019).
Coping with stigma in the workplace: understanding the role of threat regulation,
supportive factors, and potential hidden costs. Frontiers in Psychology, 1–21.
https://doi.org/10.3389/fpsyg.2019.01879
Vincent, B. (2019). Breaking down barriers and binaries in trans healthcare: the
validation of non-binary people. International Journal of
Transgenderism, 20(2/3), 132–137.
https://doi.org/10.1080/15532739.2018.1534075
Wagner, T. L., Kitzie, V. L., & Lookingbill, V. (2022). Transgender and nonbinary
individuals and ICT-driven information practices in response to transexclusionary
healthcare systems: a qualitative study. Journal of the American Medical
Informatics Association, 29(2), 239–248. https://doi.org/10.1093/jamia/ocab234

174
Wesp, L. M., Malcoe, L. H., Elliott, A., & Poteat, T. (2019). Intersectionality research for
transgender health justice: a theory-driven conceptual framework for structural
analysis of transgender health inequities. Transgender Health, 4(1), 287–296.
https://doi.org/10.1089/trgh.2019.0039
Westbrook, L., & Schlit, K. (2014). Transgender people, gender panics, and the
maintenance of the sex/gender/sexuality system. Gender & Society, 28(1), 32-57.
https://doi.org/10.1177/0891243213508008
Whipple, K. (2021). The SAGE Encyclopedia of Trans Studies. (Vols. 1-2). SAGE
Publications.https://dx.doi.org/10.4135/9781544393858
White, H., & Sabarwal, S. (2014). Quasi-experimental design and methods
(Methodological Briefs: Impact Evaluation 8). UNICEF Office of
Research.Wichinski, K. A. (2015). Providing culturally proficient care for
transgender. Nursing, 45(2), 58–63.
https://doi.org/10.1097/01.NURSE.0000456370.79660.f8
Willging, C., Gunderson, L., Shattuck, D., Sturm, R., Lawyer, A., & Crandall, C. (2019).
Structural competency in emergency medicine services for transgender and gender
non-conforming patients. Social Science & Medicine, 222, 67–75.
https://doi.org/10.1016/j.socscimed.2018.12.031
Witt, H., & Medina-Martinez, K. (2022). Transgender rights & the urgent need for social
work advocacy. Social Work in Public Health, 37(1), 28–32.
https://doi.org/10.1080/19371918.2021.1970685


