


1
Chapter 1: Introduction to the Study
African Americans are diagnosed with the human immunodeficiency virus (HIV)
at a rate higher than any other race or ethnic group in the United States of America
(Centers for Disease Control and Prevention [CDC], 2011). Some of the behaviors
associated with HIV makes it difficult to present programs to congregations. For
example, the African American population has specific attitudes, beliefs, and cultural
patterns that resist changes in behavior, particularly in the context of the traditionally
conservative South (Oster et al., 2011). Although large proportions of the African
American community are still church affiliated, the role of churches in addressing this
issue needs further research. This quantitative cross-sectional study was designed to
establish and compare the attitudes, subjective norms, perceived behavioral control, and
intentions to engage in safe sex practices (condom use or dental dam use) among adults
who have had exposure to a church-based HIV/AIDS prevention program and those who
have not.
As African Americans continue to be disproportionately affected by HIV and
acquired immune deficiency (AIDS), it has been argued that churches must not shy away
from this epidemic (CDC, 2012; Nunn et al., 2012; Timmons, 2009). Valley Christian
Church (pseudonym) is one Southern metropolitan church congregation that has
confronted HIV/AIDS by adopting a HIV/AIDS awareness campaign (see Appendix F).
Furthermore, church leaders have attempted to increase the quality and years of healthy
life of this population by reducing HIV high-risk sexual behaviors, thereby reducing HIV
incidence for African American adults as well as promoting effective public health

2
policies for HIV/AIDS prevention education.
In this chapter, I cover the background, statement of the problem, purpose of the
study, significance of the study, nature of the study, research questions, conceptual
framework, assumptions, scope and delimitations, limitations, definition of terms, and a
summary.
Background
HIV and AIDS was recognized in the United States in 1981. Since that time, the
epidemic has resulted in the loss of 659,000 lives in the United States (Kaiser Family
Foundation, 2013) and 25 million deaths worldwide (U.S. Department of Health and
Human Services, 2012). Somewhere near 35 million people across the planet currently
live with AIDS (UN AIDS, 2013). According to Moss (2013), the number of AIDS cases
increased rapidly from 1981 and declined substantially in 1995 due to the introduction of
antiretroviral therapy. Adults in racial minority communities are extremely vulnerable to
the transmission of HIV/AIDS (CDC, 2012; Wyatt, 2008).
According to the CDC, (as cited in the Morality and Mobility Weekly Report
[MMWR], 2011), a high prevalence of HIV cases exists among African Americans
disproportionally, two-and-a-half times the number of Whites (Gavan, Davis, Banks &
Bing, 2008; Wang & Aspan, 2008). Similarly, according to the CDC (2011), African
Americans accounted for an estimated 47% of all new HIV infections among adults and
adolescents in 2011 but represented only 12% of the population. The diagnoses of HIV
cases in 2012 among African Americans were seven times higher than Whites and other
ethnic groups (Alabama Department of Public Health, 2012).

3
Despite widespread efforts to curtail HIV/AIDS in the United States, southern
states such as Alabama, Florida, Georgia, Louisiana, North Carolina, South Carolina, and
Tennessee have a disproportionately higher HIV/AIDS rate than any other U.S. region
(MMWR, 2011; Wolfson, 2012). Wolfson (2012) argued that African Americans do not
adequately practice HIV/AIDS prevention strategies for several reasons, such as poor
social support systems, poor economic conditions, lack of education, decreased
motivation, drug use, and social stigma.
According to the CDC (2012), local community churches can intervene and try to
alter or improve an individual’s perceptions, attitudes, and beliefs about the personal
practices of HIV/AIDS prevention behavior. Wingood, Simpson-Robinson, Braxton, and
Raiford (2011) described a culturally tailored, gender-specific, faith-based HIV
intervention created to reduce African American women’s vulnerability to the infection
and disease. Wingood et al. (2011) found the women participants were willing to
participate in the faith-based HIV intervention, which could halt the rate of HIV cases in
the community.
The Alabama HIV/AIDS Surveillance, Public Health Report (2012) explained
that the epidemic has grown rapidly in Alabama counties. Montgomery was one of the
top five counties with the highest frequency of newly diagnosed HIV cases between 2009
and 2012 (see Table 1). The Alabama HIV/AIDS Surveillance Public Health Report
(2012) indicated that the research study conducted among racial minority groups such as
African American adults comprise one of the groups found to be exceptionally vulnerable
to HIV/AIDS due to barriers associated with poverty, lack of access to adequate health

4
care, and lack of education. The Alabama HIV/AIDS Surveillance, Public Health Report
(2012) research study was limited because it did not include stigma, discrimination and
disparity as barriers to HIV/AIDS in this population. The study contributes to the gap in
the literature because it emphasized the need for evidenced-based information to explore
the impact of HIV/AIDS on the African-American adults’ communities.
Table 1
Top Five Counties in Alabama With the Highest Frequency of Newly Diagnosed HIV
Cases, 2009-2012
County
2009
2010
2011
2012
No. (%)
Rate
No.%
Rate
No.%
Rate
No.%
Rate
Jefferson
193 (27.8)
29.3
194 (28.0)
29.5
209 (29.6)
31.7
190 (28.7)
28.9
Madison
38 (5.5)
11.3
35 (5.1)
10.5
44 (6.2)
13.4
38 (5.8)
11.3
Mobile
193 (27.8)
26.6
92 (13.3)
22.3
95 (13.4)
22.3
86 (13.0)
20.8
Montgomery
84 (12.1)
36.6
76 (11.0)
33.1
80 (11.3)
34.9
69 (10.4)
30.0
Tuscaloosa
25 (3.6)
12.31
31 (4.5)
15.9
26 (3.9)
13.4
33 (5.0)
17.0
Note. From, “State of Alabama HIV Surveillance Annal Report Finalized 2012,” by
Alabama Department of Public Health, Division of HIV/AIDS Prevention and Control.
Given the strong historical and cultural connections between the African
American community in the American South, particularly the Southern evangelical
denominations, churches appear to be institutions well positioned to understand the
HIV/AIDS problem in the broader community. For example, Berkley et al. (2010)

5
described a health intervention program called “TIPS: Taking it to the Pews,” funded by
the Ministry AIDS Initiative, to reduce the number of HIV cases throughout Alabama.
Bertly-Patton et al. (2013) also explained that churches equipped with easy-to-deliver
HIV tools may be in a position to provide church appropriate screens, education, and
support services to their congregations. Furthermore, the CDC (2012) claimed that local
community churches are ideally situated to provide guidance and support to individuals
by making appropriate education a routine part of their church ministry risk reduction and
prevention program to combat HIV/AIDS stigma.
Researchers have considered various aspects of programs and strategies that may
be relevant to the African American community including prevention programs
strategies, teen AIDS church prevention programs, gender related concerns related to
HIV/AIDS prevention strategies (Wechsberg et al., 2010), addressing HIV/AIDS from
the pulpit (Francis & Liverpool, 2009), AIDS knowledge counseling and skills building
courses program evaluation (Francis & Liverpool 2009), HIV/AIDS and substance abuse
programs (Wechsberg et al., 2010), role playing as it relates to communication skills
(Adimora, Schoenbach, & Floris-Moore, 2009), HIV transmission (Merson, O’Malley,
Serwadda, & Apisuk 2010), and HIV/AIDS facts, abstinence, and condom use (Darbes,
Crepaz, Lyles, Kennedy, & Rutherford, 2008).
Consequently, in this study I analyzed information about two similar Christian
churches in a major southern city--one church with an HIV/AIDS prevention program
and one without an HIV/AIDS prevention program. The study was needed to increase
one’s knowledge that church leaders and program planners can develop specific church-

6
based HIV/AIDS prevention interventions suited for adults living in similar demographic
areas. Involving adults in health prevention programs can be invaluable to the
development and delivery of community, church-based HIV/AIDS prevention program
strategies (Massey, 2010).
Statement of the Problem
HIV/AIDS continues to be a major public health problem among young and older
adults (CDC, 2009), and there is a higher incidence of HIV/AIDS and higher mortality
rate among African American adults compared to other groups (CDC, 2012). Research
has suggested that contemporary sexual practices and mores are key to reducing HIV
infection (Crepaz, 2009; Darbes et al., 2008; Finlayson et al., 2011; UNAIDS, 2013) and
that risky behavior is central to the discussion of and solution to the skewed rate of
infection in that community compared to the nation as a whole. To a significant extent,
the higher incidence of HIV among African American adults related to sexual risk
behavioral practices can be reduced through an increase in knowledge and perceptions
about how to prevent the illness and disease. However, there are no evidence-based,
church developed culturally sensitive HIV/AIDS prevention strategies for African
American adults (Higgins, 2010). The results of this study helped fill the gap in the
literature by possibly identifying future public health policies that could promote
effective HIV interventions based on specific cultural and behavioral patterns observed
among this particular population.

7
Purpose of the Study
The purpose of this quantitative cross-sectional study was to establish and
compare attitude, subjective norm, perceived behavioral control, and intention (see
definitions) relative to condom and dental dam usage, among adults within two church
communities: one with an HIV prevention program and one without. The study was
designed using the theory of planned behavior (TPB) conceptual framework, which infers
that intention is the primary determinant of behavior and is particularly influenced by
attitudes, subjective norms, and perceived behavioral control.
This study filled an existing gap in the research literature for this particular
population because there is limited literature on HIV/AIDS prevention programs for
church-attending adults in the South. The present study may also promote additional
research concerning specific educational interventions targeting adult populations and
other local church group communities. Exposure to the church-based HIV/AIDS
prevention program for adults was the study’s independent variable. The main dependent
variables included the attitude toward behaviors, subjective norm, perceived behavioral
control, and intention.
Research Questions and Hypotheses
Exposure to the church-based HIV/AIDS prevention program for adults was the
study’s independent variable. The dependent variables included the attitude toward
behavior, subjective norm, perceived behavioral control, and intention. The covariates or
control variables were church status, age, gender, marital status, ethnicity, education
attainment, and household income. Based on a review of the literature, four hypotheses

8
guided the analysis of data. In addition, the following research questions (RQs) were
addressed via the quantitative cross-sectional study.
1. To what extent does exposure to a church-based HIV/AIDS prevention
program influence attitude, subjective norm, and perceived behavioral
control of adult Christian church attendees in the South?
2. To what extent does exposure to a church-based HIV/AIDS prevention
program influence intention to engage in safe sex practices (condom or
dental dam use) of adult Christian church attendees in the South?
H01: There is no statistically significant difference between attitude scores towards
condom use or dental dam use for individuals who have participated in a
church-based HIV/AIDS prevention program and those who have not.
HA1: There is a statistically significant difference between attitude scores towards
condom use or dental dam for individuals who have participated in a
church-based HIV/AIDS prevention program and those who have not.
H02: There is no statistically significant difference between subjective norm
scores towards condom use or dental dam for individuals who have
participated in a church-based HIV/AIDS prevention program and those
who have not.
HA2: There is a statistically significant difference between subjective norm
scores towards condom use or dental dam for individuals who have
participated in a church-based HIV/AIDS prevention program and those
who have not.

9
H03: There is no statistically significant difference between perceived behavioral
scores towards condom use or dental dam for individuals who have
participated in a church-based HIV/AIDS prevention program and those
who have not.
HA3: There is a statistically significant difference between perceived behavioral
scores towards condom use or dental dam for individuals who have
participated in a church-based HIV/AIDS prevention program and those
who have not.
H04: There is no statistically significant difference between intention scores
towards condom use or dental dam for individuals who have participated in a
church-based HIV/AIDS prevention program and those who have not.
HA4: There is a statistically significant difference between intention scores
towards condom use or dental dam for individuals who have participated in a
church-based HIV/AIDS prevention program and those who have not.
Conceptual Framework of the Study
The study established and compared attitudes, subjective norms, perceived
behavioral controls, intentions to engage in safe sex practices, and sociodemographics
relative to sexual risk behaviors of adults who attended church services. The TPB,
originally developed in the 1960s as the theory of reasoned action, predicts a person’s
intention to behave in a certain way. The model evolved from the field of social
psychology and has been modified over the years. This systematic method was based on
a sequence of events and has been used to predict whether an individual will seek

10
interventions to prevent HIV or not. For example, an individual’s attitude is based on past
experiences, whether positive or negative, as well as his or her beliefs and norms (Ajzen,
2011). The TPB has been used to explore why some people practice safe sex and others
do not (Glanz & Viswanath, 2008; Mausbach, Semple, Shathdee, & Patterson, 2009;
Montano & Kasprzyk, 2008).
The TPB was viewed as potentially useful in predicting the person’s actions
regarding health by focusing on the individuals’ behavior, normative beliefs, attitudes,
motivations to comply, subject norm, and the intention to perform the behavior (Ajzen,
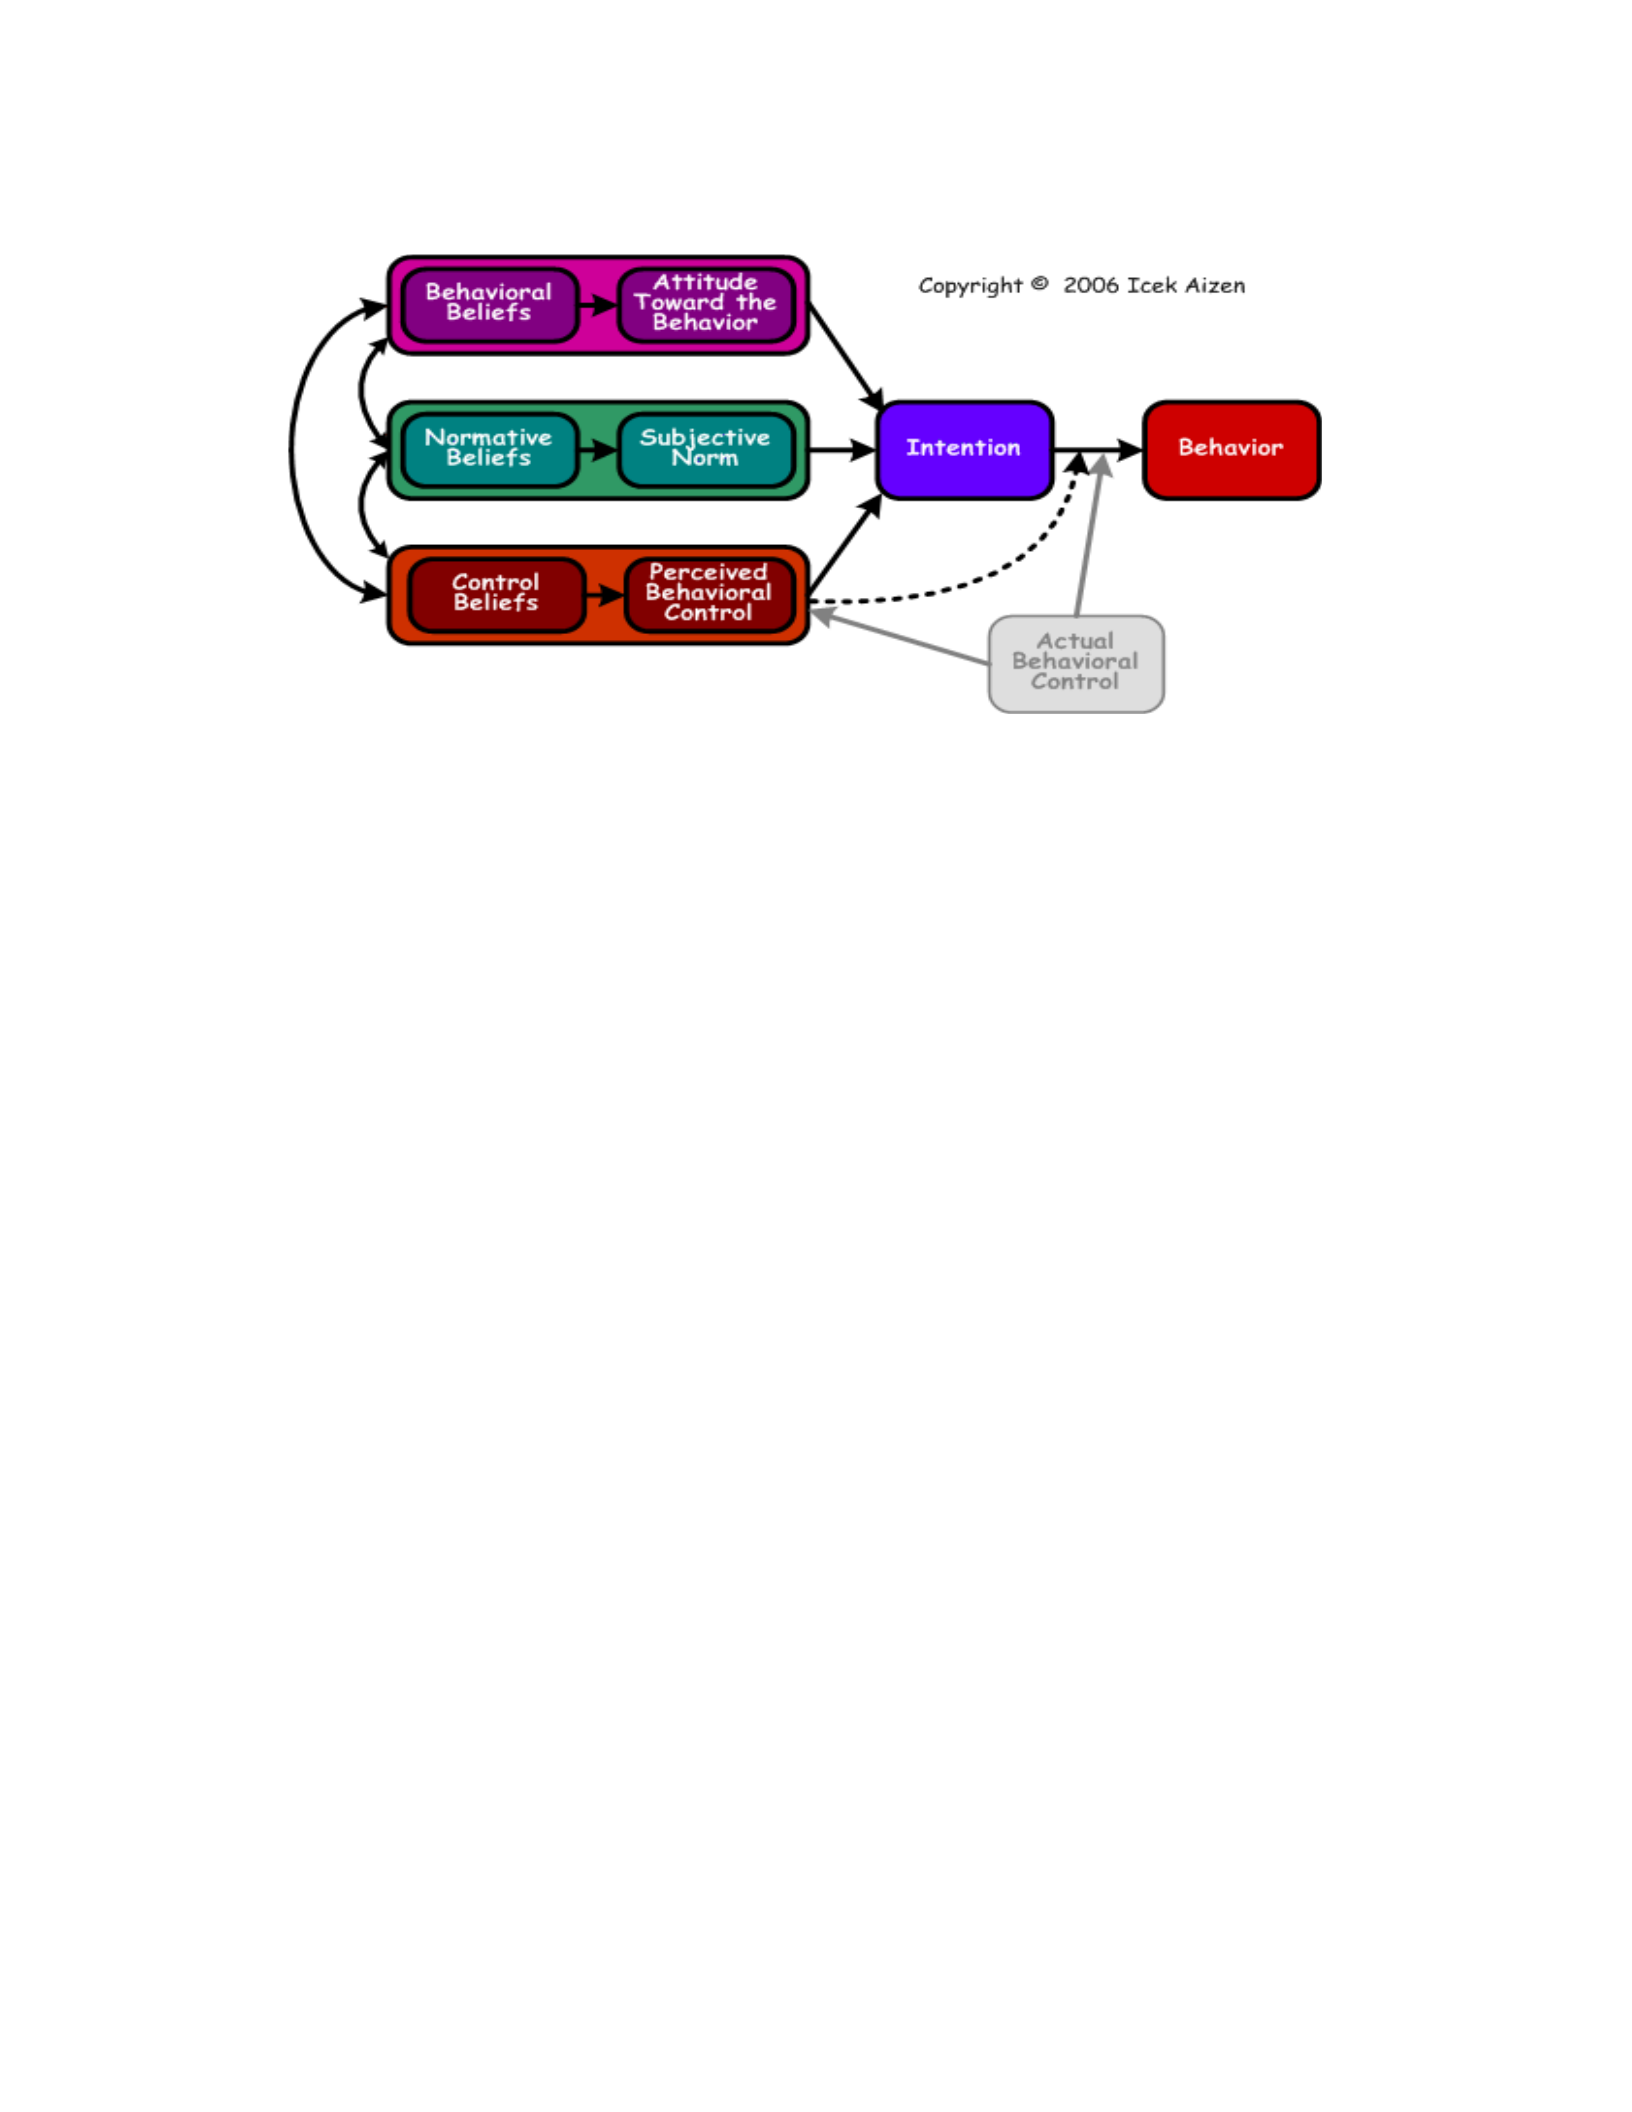
2011). According to the TPB (see Figure 1), three considerations guide human action: (a)
the individual’s belief about the likely outcome of the behavior, (b) the individual’s
evaluation of the outcomes, and (c) the individuals’ belief about what others normally
expect, as well as the motivation to comply with those expectations (Ajzen, 2011).
Weiner (2010) posited that three principles guide one’s behavior. For example,
the person must be motivated to embrace the need to achieve certain concepts. In
addition, the person has to have either pleasure or pain as an incentive to change the
behavior or expect that the value (high or low expectancy of success) of the incentive is
worth it to determine if the person will carry out the achievement. Weiner asserted that
the less difficult the task, the more behavior consistently follows social norms; the more
difficult the task, the less consistency there is with alignment of behavior and social
norms. Figure 1 shows the schematic presentation of the theory of the planned behavior.
11
Figure 1. An example of the theory of planned behavior. Reprinted from
www.people.umass.edu/aizen/tpb.html. Retrieved July 21, 2013. Copyright 2006 by
I. Ajzen. Reprinted with permission.
Limitations of the Theory of Planned Behavior
The TPB was limited in measuring other factors such as culture, socioeconomic
status, previous experiences, and environmental factors that may influence health
behaviors. Therefore, African Americans experience the effects of barriers and other
factors outside of their control, which can influence the likelihood of their seeking
HIV/AIDS counseling, testing, early medical treatment, and healthy sexual practices. In
addition, the TPB was limited in terms of predicting involuntary behavior.
Although an individual may strongly intend to carry out a specific behavior, the
individual may not perform the act necessarily because of the opportunities, resources, or
ability (Ajzen, 2011). The TPB has been long regarded as the universal model of
behaviors of social relevance that are under the person’s volitional control. This model is
thus able to predict the most accurate behavior by measuring intentions, which is the
immediate determination of behavior and perceived behavior control (Ajzen, 2011). A
more detailed explanation will be provided in Chapter 2.

12
Nature of the Study
The research design was established and compared attitudes, subjective norms,
perceived behavioral control, and intention, variables relative to adults within a
comparable population of two Christian church groups. The TPB questionnaire
developed by Ajzen in 1985 was adapted for this study. The modified TPB questionnaire
(Appendix F) contained a variety of dependent variables to measure, such as attitudes,
subjective norms, perceived behavior control, and intentions to use condoms or dental
dams among adults. The independent variable was the exposure to a church-based
HIV/AIDS prevention program. The covariates or control variables included
sociodemographics, church status, age, gender, marital status, education attainment, and
household income.
In addition, the quantitative cross-sectional study design was chosen over other
designs based on its best fit to focus on individual experiences. This allowed me to
investigate the problem and give credence to my ultimate findings. The quantitative
cross-sectional study consisted of distributing the TPB questionnaire to participants to
learn more about the attitudes, subjective norms, perceived behavior control, and
intentions relative to safe sexual behaviors of adults. The TPB can help provide the
structure for identification and measurement of the factors that affect sexual behavior.
Definitions
Abstinence: A health, religious, moral, or legal choice to refrain from sexual
intercourse, which includes oral, vaginal, or anal sex (Rossi, 2009).

13
Acquired Immunodeficiency Syndrome (AIDS): Progressive failure of the immune
system causes the infected person to die from either malignancies or opportunistic
infections (CDC, 2009).
Attitudes: A consistently favorable or unfavorable response to a stimulus
(Altmann, 2008).
Church-based HIV/AIDS prevention program training: A church ministry that
provides training related to HIV/AIDS prevention to local community residents with
special focus on healing, prevention, and empowerment (Godwin et al., 2012).
High risk sexual behavior: Individuals with an increased risk of acquiring HIV
through sexual encounters, including men who in the past year have had sex with other
men, men and women who have had sex with more than one partner, individuals who
have knowingly had sex with an HIV infected person, or those who have exchanged sex
for drugs or money (CDC, 2011).
Human Immunodeficiency Virus (HIV): A retrovirus that occurs after the transfer
of body fluids from an infected person to an uninfected person and lead to AIDS (CDC,
2011).
Intention: A person's motivation to perform a specific behavior (Ajzen, 2011). An
intention is based on attitude, subjective norm, and perceived behavioral control toward
the behavior and usually precede behavior.
Perceived behavioral control: Refers to an individual’s perception of his or her
ability to perform a specific behavior (Ajzen, 2011).

14
Sexual risk behavior: A sexual practice that may increase the probability of
contracting a disease, such as HIV/AIDS (CDC, 2012).
Sociodemographics: The sociodemographics profile of the studied population
consists of church status, age, gender, ethnicity, marital status, education attainment, and
household income.
Stigma: A discrediting judgment that is expected by an individual or group to
exclude interactions from others in society (Bos, Pryer, Reeder, & Stutterheim, in press).
Subjective norm: According to Ajzen (2011), it is the perceived social pressure to
engage or not engage in a behavior.
The Balm in Gilead: A not-for-profit, nongovernmental organization located in
New York City. It is the only organization in the United States that is dedicated to
empowering churches in the struggle against HIV/AIDS in African American
communities (Harris, 2010).
Theory of planned behavior (TPB): A conceptual framework for understanding
predicting intentions and behavior (Ajzen 2011).
Assumptions
Adult church members were assumed to be willing to participate in the study and
give honest responses to the (TPB) high-risk sexual behavior survey. It was further
assumed that adults who represented a diverse cross-section of church-going Christians
would trust me as the researcher and openly and truthfully indicate their attitudes about
HIV/AIDS, subjective norms, perceived behavioral controls, and sexual risk behaviors.

15
Another assumption was the church-based HIV/AIDS prevention program was one of the
primary sources of information on the topic for the participants in the study.
Scope and Delimitations
This study employed quantitative study measurements and assessments to
establish and compare the outcomes related to the participants’ attitudes, subjective
norms, perceived behavioral controls, intentions, and sociodemographic variables relative
to sexual risk behaviors of a church-based HIV/AIDS prevention program experimental
group to a control church group. This study was delimited to adults who (a) attended a
Christian church in the South, (b) identified themselves as being 18 years old or older,
and (c) able to read and write in English.
This specific focus was chosen to establish and compare the attitudes, subjective
norms, perceived behavioral controls, intentions and sociodemographics relative to
sexual risk behaviors among adults, which predisposes them to HIV/AIDS. Single group
threats to internal validity were ruled out in this study because the second group was a
control group and was comparable to the program group. The study took place at two
different churches with different people and at different times. The external validity
(ability to generalize) may not be strong because the study employed a nonrandom
sample.
Limitations
The study was limited to adult members of two churches in one mainline
Christian denomination. A second limitation was that the data were not collected on the
participants’ attitudes, subjective norms, perceived behavioral control, intentions, and

16
sexual behaviors of adolescents. Self-reporting was another limitation to this study
because there may have been some participants who underreported actual experiences. In
addition, all participants were informed that all data would be kept completely
confidential. Consequently, this study did not include adults in other HIV/AIDS
prevention programs.
Researcher Bias
I am an adult in the age group of those being studied, who attends a local church,
and has experience with the challenges of being at risk of acquiring HIV/AIDS. To the
best of my ability, I did not allow my opinions to effect the administration or outcome of
the research. The use of a quantitative research instrument also helped insulate the
study’s data collection from my personal biases.
Significance of the Study
The present study provided new data on the current attitudes, subjective norms,
and perceived behavioral control and intentions about the sexual risk practices among a
specific population of church-going adults in the South. The results of this study serve to
identify future public health policies that can promote effective HIV prevention offered at
community churches, provided practitioners, and professional peers with important
feedback about short and long-term performance. More specifically, existing data about
HIV point to a considerable risk of infection among all sectors of the adult population.
The conclusions arising from this study served to address behaviors conducive to HIV
that are believed to be generalizable to the adults in Southern states.

17
In addition, the study addressed the barriers and obstacles to developing and
implementing appropriate and culturally sensitive HIV prevention strategies within this
population. The study was significant because its results argued for supporting and
promoting health education, early detection, and testing for HIV/AIDS.
Summary
In Chapter 1, I addressed the problem facing the adult community in the South
with respect to high infection rates and severity of the effects of HIV/AIDS. This study
was established and compared exposure to a church-based HIV/AIDS prevention
program and one without relative to attitudes, subjective norms, perceived behavioral
control, and intentions among adults. The conceptual framework was the TPB, and a
questionnaire was proposed and adapted from the work of Ajzen (2011). In this chapter, I
discussed assumptions, limitations, and the potential biases of the researcher. In the
following chapter, I will explore the existent literature on HIV/AIDS with respect to its
effects on the adult community in the South, and more specifically, the research to date
on prevention, education, and treatment within that church community.

18
Chapter 2: Literature Review
Introduction
The research problem is that there are higher incidences of HIV/AIDS among
African American adults compared to other groups. In addition, there is an increased risk
of diagnosis with advanced stage HIV/AIDS and a higher mortality rate among African
American adults who are diagnosed with HIV/AIDS. Finally, there are no evidence–
based, culturally sensitive, and appropriate HIV/AIDS prevention strategies for African
American adults. Therefore, the basic purpose of this quantitative cross-sectional study
was to establish and compare attitudes, subjective norms, perceived behavioral control,
intentions and sociodemographics relative to sexual risk behaviors of adults within two
local Christian church communities: one with a program and one without.
In the literature review, I describe the attitudes, subjective norms, perceived
behavioral control, intention and sociodemographics relative to church-based HIV/AIDS
prevention education as an alternative to other means of reaching targeted populations at
high-risk of acquiring and transmitting HIV. Numerous studies have suggested African
American adults are disproportionately infected and affected by the HIV/AIDS pandemic
and have higher rates of infections than other races (Alabama Public Health Report,
2012; CDC, 2012; El-Bassel, Caldeira, Ruglass, & Gilbert, 2010; Harris, 2010; Henny et
al., 2012; Hosek, Brothers, & Lemos, 2012; Kennedy, 2011; O’Brien, Bayoumi, Davis,
Young & Strike, 2009; Radcliffe et al., 2010).
More than 750 studies were identified in August 2013 via Walden University’s
Thoreau multiple databases, Medline, PsycINFO, and Google Scholar computer searches

19
using key words such as knowledge, attitude to AIDS, condom and HIV, stigma and HIV,
church-based HIV/AIDS prevention, HIV risks, behavioral risk factors related to
community church outreach and education programs, church-based health programs,
HIV interventions, church and HIV knowledge, HIV prevention programs, and HIV
infections; however, only specific research studies that are relevant to this study were
included in the dissertation. The search also included published and peer-reviewed
articles that contained questionnaires related to attitudes, perceived behavioral control,
and intentions to engage in safe sex practices (condom or dental dam use) about sexual
risk behaviors relative to African American adults.
In addition, published and peer-reviewed articles were reviewed that related to
the factors that may influence safe sex practices and church engagement in providing
insight about HIV/AIDS prevention. The published and peer-reviewed articles reference
lists were examined for additional relevant articles that were not found in prior searches.
The literature search began in March 2006, was repeated in April 2007, and once more in
August 2013 to identify new articles.
Organization of the Literature Review
In this chapter, I first describe the TPB theoretical foundation as it relates to HIV
and the African American population. I examined quantitative and qualitative studies that
showed the extensive use of the TPB questionnaire for other different behaviors. The
chapter reveals the literature that described the use of TPB constructs to study behavior
among adults. In addition, the literature was searched for articles describing validated
instruments for use in research to identify knowledge deficits and evaluate risk reduction

20
strategies and treatment programs. Other articles furnished guidelines useful in
developing an instrument to test TPB constructs. Ajzen (2011) provided the platform for
the survey in the areas of attitude, subjective norm, perceived behavioral control,
intention and sociodemographics relative to exposure to a church-based HIV/AIDS
prevention program.
Theoretical Foundation
The strategy of this research was to use the TPB (Ajzen, 2011) to establish and
compare the constructs of attitudes, subjective norms, perceived behavioral controls, and
intentions to engage in condom use or dental dam use relative to sexual risk behavior
among adults who were exposed to a church-based HIV/AIDS prevention program and
those were not. In addition, the TPB has been used to determine the relationship between
young adults aged 15 to 24 years old and their attitudes about intentions to use condoms
(Hallub, Reese, Herbenick, Hensel, & Middlestadt, 2011). Similarly, Rhodes, Al-oballi,
and Penprose (2011) described the use of the TPB in understanding overweight
adolescents’ beliefs. The TPB has been frequently used to understand employees’ hiring
intentions in regard to qualified workers with disabilities (Fraser, Ajzen, Johnson, Hebert,
& Chan, 2011) and to understand binge drinking of college students (French & Cooke,
2012).
Ajzen (2011) explained that normative beliefs are the expectations of others and
the motivation to comply with those expectations. Additionally, Ajzen argued that when
an individual is ready to perform a specific behavior, he or she will first show a sign of
intention to engage in the behavior. The behavioral beliefs include the individual’s beliefs

21
and the outcomes, such as any unprotected vaginal or anal sex or unknown HIV infection
status.
Other theories were considered for use in the study such as the AIDS risk
reduction model (ARRM), the health belief model (HBM), and the stages of change
model. The ARRM was introduced in 1990 and incorporates variables from HBM,
diffusion of innovation model, and social cognitive theory to explain the behavior change
of individuals who are diagnosed with HIV/AIDS (Durojauye, 2011). HBM is one of the
conceptual frameworks that has been used for many years to explain health behavior
(Sharma, 2011). This theory was developed to understand the lack of the individual’s
participation in health screening and prevention programs. The specific variables used in
this theory include perceived threat, perceived benefits, perceived barriers, and cues to
action as well as self-efficacy.
The stage of change model was developed by Prochaska and DiClemente in the
1990s to address smoking cessation (Okpaku, MacMaster, Dennie, & Tolliver, 2008).
This theory uses six stages of change from major theories to describe what an individual
must overcome in an effort to change a specific behavior such as precontemplation,
contemplation, preparation, action, maintenance, and relapse (Okpaku et al., 2008).
All the theories discussed above have specific limitations. For example, the HBM
model does not include the influence of social norms and peer influence on an
individual’s decisions regarding health behaviors. ARRM does not consider sociocultural
issues that influence an individual’s actions. The stages of change model does not take
into account environmental or structural problems related to effects of particular

22
behaviors. In comparison, the TPB model can help individuals to identify and measure
factors that affect sexual risk behaviors such as attitudes that put one at risk of acquiring
HIV.
Attitude
According to Ajzen (2011), a behavioral belief occurs when the individual’s
belief is associated with a particular behavior that has positive or negative consequences.
Therefore, the behavior will be dependent on the individual’s accessible behavioral
beliefs (Ajzen, 2011). Boileau, Rashed, Selim, Sylla, and Zunzune (2008) sought to
validate an instrument to monitor HIV risk and interventions of urban West African
youths. In the study, a HIV/AIDS behavioral surveillance instrument was developed. The
validation sample (N =342) and the exploratory sample (n =189) of men and women were
interviewed face-to-face. Attitudes and perception of behavioral control was associated
with gender, sexual experience, and education. In addition, condom use was significantly
predicted from attitudes, perceived behavioral norms, and communication with peers.
The study concluded that the questionnaire was valid and reliable, which makes it a
valuable tool to assess youth’s sexual risk behavior in an urban setting in West Africa.
Wang (2009) argued that more detailed theoretical explanation and more precise
guidance relative to prediction of behavior can be found when the TPB integrates attitude
functions. Undergraduate students (N = 549) were sampled to determine if individual
intentions to participate in physical activity on a regular basis was predicted based on the
individual’s self-esteem maintenance attitudes. The effects of this phenomenon were
moderated via the individual’s self-esteem and self-monitoring strength. The study

23
concluded that campaign planners could use more detailed attitude constructs to design
campaign messages to specific populations.
Subjective Norm
Mirkuzie, Sisay, Moland, and Astrom (2011) conducted a study in Addis Ababa
to explain HIV testing in an antenatal setting by applying the TPB questionnaire. The
HIV counseling and testing were offered routinely to prevent mother-to-child
transmission of HIV. The study used a sequential exploratory mixed methods approach.
The sample included (N = 3,033) women who completed the TPB questionnaire while
2,928 participants completed the follow up of actual HIV testing. The data were analyzed
using descriptive statistics, such as chi-square tests, linear regression, and Pearson
correlation. Subjective norm indicated that there was substantial amount of variance in
intentions and attitudes. The TPB explanation power was found to be low due to the large
proportion of participants who intended to get tested for HIV. The study concluded that
social approval can provide positive consequences for women and should be told upfront
that they can choose to opt out to improve prevention of mother-to-child transmission
services.
In another study, Abamecka, Godesso, and Girma (2013) conducted cross-
sectional quantitative institutional research among a sample of 336 health professionals
from selected districts of Jimma, Ethiopia, in 2012. The TPB was self-administered, and
the constructs were measured to predict the role of the independent variables. A
multivariable linear regression model was used and data were entered into the SPSS
version 16.0 for analysis. The study determined that the strongest predictors of intention

24
to volunteer HIV counseling and testing (VCT) were subjective norm (β=0.39, p <0.001)
and attitude (β= 0.19, p <0.001) while the sociodemographic variables did not reveal
significant prediction of the intention to use VCT.
Participants who had experiences past VCT did not have significant statistical
association with intention. The study concluded that a function of attitude and perceived
behavioral control was based on the intention to perform the behavior. This study sought
to empower health professionals to change negative attitudes about VCT, and determined
that demographic related social determinants were not barriers to use of VCT.
Furthermore, Miner, Peterson, Welles, Jacoby, and Rosser (2009) examined the
association between social norms and unsafe sexual practices. The sample consisted of
675 HIV infected men who had sex with men and were enrolled in a community-based
organization HIV risk behavior program. The study mentioned that the theory of
reasoned action (TRA) describes use of a condom as being dependent upon one’s
intentions to use it. Baseline data were collected via self-reports between January 2005
and April 2006. The participants were recruited from Boston (n = 64), Houston, (n =
103), New York (n = 177), Seattle (n = 114), and Washington, DC (n = 71). Participants
were included in the study if they spoke English, were HIV positive, were at least 18
years old, had anal sex without a condom in the past 12 months, and had sex with at least
one man in their lifetime. African American participants comprised 45% of the sample,
Whites were 23%, and Latino/Hispanics along with Asian/Pacific Islanders as well as
mixed races were only 7%.

25
The study was limited because the participants were from a convenience sample
versus a random sample of HIV-positive men. The data were collected via self-report,
which indicated that the sexual behavior information collected were over a 3-month
period, retrospectively. The study concluded that the TPB increases understanding about
safe sex and their belief that they can control the specific behavior.
Perceived Behavioral Control
Ajzen (2011) argued that perceived behavioral control occurs when a people
perceive they can perform a specific behavior. Perceived behavioral control is determined
by beliefs about the presence of influences that may help the individual achieve or avoid
the performance of a specific behavior. More specifically, perceived behavioral control
can be used along with intention to predict a particular behavior.
Kiene, Tennen, and Armeli (2008) attempted to explain the variability in condom
use attitudes, self-efficacy and behavioral intentions that can vary day-to-day. The sample
included (N = 116) sexually-active college students, during a 3-week period of 1
semester, who reported their current feelings of negative effect as it related to their
condom use attitudes, self-efficacy, and behavioral intentions and sexual behaviors for
day-to-day changes for the previous 30 days using a web-based structured daily diary in
order to design effective interventions that would lead to increase condom use.
Of the 116 participants, 49 were male and 67 were female undergraduates with an
average age of 19.15 (SD = 1.51). A majority of the participants (88.9%) described
themselves as White/European-American, 5.1% as Black or African American, 3.4% as
Asian American, 1% as Latino or Hispanic, and 1.7% as another ethnicity. All of the

26
participants described themselves as either not being married, but in a dating relationship.
A z-test (p < .001 for all tests) was used to evaluate within-person variance for all of the
social cognitive variables and was found to be statistically significant. The percentage of
total variability that was within-persons for attitudes was 13.85%. Behavioral intentions
were 14.65% and 13.78% for self-efficacy. Gender for daily condom use, the moderator
variable, did not moderate the effect of daily attitudes or the effect of daily behavioral
intentions (Kiene et al., 2008).
In the context of gender differences, women’s condom use was less likely with
casual partners than with steady partners, but for the men, the condom use was less likely
with steady partners. Failure to use condoms was associated with attitudes, self-efficacy
(perceived behavioral control), and behavioral intentions on a day-to-day basis. The study
concluded that individuals who tended to have stronger behavioral intentions than those
who tended to have weaker behavioral intentions increased the likelihood of condom use.
Although the study was limited by not including a partner’s influence in condom use
decision-making, it provided a clearer understanding of the predictors of condom use
(Kiene et al., 2008).
Carmack and Lewis-Moss (2009) conducted a cross-sectional TPB study to
examine behavioral intention condoms. The study included 462 African American
adolescents’ ages 12 to 17 recruited from a Midwestern U.S. city and its surrounding
areas about their attitudes, norms, perceived control, and intention regarding condom use.
Fifty-six percent (n = 250) of the participants were female. Forty-seven percent (n =217)
of the participants were in the ninth grade. Twenty-eight percent (n =129) were in the 10th

27
grade, and 25% (n =116) were in the 11th or 12th grade. The study used the TPB with this
population to assess whether these adolescents intended to engage in protected sexual
relations (condom use) in the following year. This may have important implications in
dealing with adolescent sexual behavior, such as increasing intentions to use condoms.
Perceived behavioral control was found to have the ultimate influence on
intention with regard to sexual behaviors and African American adolescents. The study
found that the effect-indicator model showed a control increased, self-efficacy increased
(standardized γ = .900, p < .001), but perceived controllability decreased (standardized γ
= –.333, p < .001). The results suggested that an African American adolescent's self-
reported control coincides with his or her perception of decreased availability of condoms
but would increase depending upon the situation such as a specific ability to use a
condom with a particular partner (Carmack & Lewis-Moss, 2009).
The study was beneficial because it showed that increasing self-efficacy in
African American adolescents could lead to the development of interventions that focus
on the situation-specific abilities of African American adolescents to negotiate condom
use. Negotiating condom use with a partner can have a greater influence in the person’s
intentions to use condoms during sex, thus influencing actual condom use. The study was
limited because it did not address indications of past condom use behavior for adults,
which would add to the theoretical power of the TPB in terms of influencing intention.
HIV/AIDS Education and Awareness in African American Churches
Church-based HIV/AIDS education to increase awareness about the infection and
disease is important to open discussion about risk reduction behavior. Ellison, Musick,

28
and Henderson (2008) found that although African Americans experience below average
socioeconomic status, their connection to church traditions increases psychological well-
being. There is mounting evidence that HIV/AIDS has taken a measurable toll on the
health and well-being of African American adults and other racial/ethical minorities and
churches are getting involved in the fight against the disease (CDC, 2012; Nunn et al.,
2012).
According to Wingood et al. (2011), community church leaders are being
educated about how best to integrate HIV/AIDS prevention messages in their sermons
and prayers as well as incorporate effective HIV/AIDS prevention programs. The
HIV/AIDS epidemic has grown rapidly as research studies conducted among racial
minority groups indicated that African American adults comprise one of the groups found
to be exceptionally vulnerable to HIV/AIDS due to barriers associated with poverty, lack
of adequate health care, and lack of education (Arya, Behfovor, & Viswanath, 2009;
Timmons, 2009).
Timmons (2009) explored factors related to implementing research-based health
programs in church settings in South Carolina with pastors from 11 Christian churches.
Of the 11 churches, seven pastors participated in Group 1 and four in Group 2. The
qualitative methodology used to address the research questions were focus groups and
semistructured interviews. Timmons used a constant comparative method to analyze the
coded transcripts and categorized data themes. Findings suggested program planners need
guidance in designing effective community level measures to disseminate information
that assists in increasing awareness of particular relevance to HIV prevention. The study

29
was limited in scope because it did not include other church denominations, which made
the results generalizable only to the Christian church community. The study provides
insight into what religious leaders know about HIV/AIDS, and adds to the literature gap
of knowledge about developing appropriate church-based HIV/AIDS prevention
messages.
In addition, Timmons (2009) suggested that when research is conducted in
partnership with African American churches to implement research-based health
programs, the congregant needs, pastors, and researchers have a common understanding
of the particular study, the specific shared program ethics can play an essential role in
generating successful outcomes. Although this research was generalizable only to the
sampled population, it adds to the body of knowledge that programs designers can use to
create and implement HIV/AIDS prevention strategies that could be suited for African
American adults to increase their quality and years of life. Additional research regarding
the factors related to implementing research-based health programs in church settings
could strengthen these research findings.
Nunn et al. (2012) conducted research on HIV prevention in 38 faith-based
institutions in Philadelphia. The study was chosen to highlight the perceived barriers and
recommendations to encourage African American faith leaders to engage in HIV/AIDS
prevention education and training. African American pastors participated in five focus
group discussions about the challenges in addressing HIV/AIDS, and the factors that
contribute to the epidemic. Some of the faith leaders were concerned about the fear of

30
losing parishioners, not having appropriate educational information, in terms of
discussing HIV/AIDS and human sexuality from the pulpit.
The findings suggested that HIV/AIDS prevention developed by CDC may not fit
the church-based setting and should build collaborative partnerships between public
health and faith-based institutions that promote abstinence and delayed sexuality activity.
The study was limited by the fact that half of the sampled population was based upon the
churches that had an existing relationship with the Major’s Office of Faith Based
Initiatives investigator, which did not represent the African American National faith-
based community. The CDC (2012) studied Alabama churches that work to promote
HIV/AIDS prevention education.
According to CDC (2012) pastors at 11 African American Christian churches
provided prevention education to their congregations to combat HIV/AIDS stigma. The
intervention program was entitled “TIPS: Taking it to the Pews.” The Alabama Council
on Substance Abuse operates TIPS in Alabama. In addition, CDC (2012) estimated that
many African-American adults living in Alabama do not know their HIV status. CDC
further reported that during 2012, African Americans comprised 26% of Alabama’s
population while 68% were newly diagnosed with HIV infection. CDC estimated that the
newly diagnosed HIV infections occurred with adults 25 to 44 years old (46%). Thirty
percent of the HIV infections occurred with individuals that were between 15 and 24
years old.
Overall, the majority of adults who were living with HIV were between 45 and 64
years old (CDC, 2012). Montgomery County was one of the five ranked with the highest

31
rate of HIV infection each year between 2008 and 2012. This study suggested that
African American pastors are educating their congregations about HIV/AIDS prevention.
In addition, the study showed there were positive outcomes such as many of the
congregants getting tested for HIV. The study added to the gap in the literature about
HIV/AIDS prevention education for African American adults at greater risk of acquiring
the disease and determining that knowing one’s HIV status is extremely important in
reducing the HIV/AIDS cases in the South.
Manley et al. (2011) conducted qualitative research via face-to-face interviews
with a final sample of 1,142 HIV infected women and 511 HIV uninfected women to
determine if cognitive impairment effects brain function in HIV positive females. Manley
et al. found that ethnic groups are often misdiagnosed due to cognitive impairments. The
relationship of demographic factors was also examined from both HIV and non-HIV
infected women. The findings showed there was a relationship between ethnicity, age,
education, and reading level speed as well as executive functioning among HIV positive
and HIV negative African-American women.
African Americans and Lack of Personal-Centered Mission
Although AfricanAmericans view the church as a gatekeeper of support in their
community and churches are recognizing their role as essential players in the fight
against HIV/AIDS, one factor that is important is the congregants’ dialogue about their
experiences (Timmons, 2009). In contrast, Lindley, Gaddist, and White (2010) conducted
a cross-sectional research study in South Carolina during 2007, with 1,445 congregants,
61 pastors, and 109 care team members.

32
Lindley et al. found that the congregants were not knowledgeable about
HIV/AIDS transmission by casual contact. For example, HIV is not transmitted by day-
to-day contact in a social setting, the workplace, or schools nor is HIV transmitted
through casual kissing, shaking hands, or hugging. One cannot become infected with HIV
from food, dishes, drinking glasses, a drinking fountain, door knob, from a toilet seat, or
pets with HIV (Lindley et al. 2007). In addition, older adults 65 years old or greater were
less knowledgeable about HIV/AIDS transmission and significant high levels of HIV-
related stigma than younger adults. The authors concluded that churches should reinforce
education about the ways that HIV can be transmitted by adult males and older people.
The limitations of the study included a lack of discussion about HIV transmission by
females and strategies to reduce stigma. The findings are supportive of HIV prevention
efforts targeting church-based HIV/AIIDS prevention for adults.
Behaviors Associated With HIV/AIDS Status
Several modes of exposure place African American adults at risk of contracting
HIV. For example, Noor, Ross, Lai, Dejian and Risser (2013) used a collaborative driven
effort of a nonrandom sample selection of their peers. Eligibility criteria consisted of
participants being 18 years of age and older who lived in the city of Houston, TX, or
Harris County and injected drugs within the most recent 12 months. CDC (as cited in
Noor et al., 2013) estimated that both unsafe risky behavior and drug-using practices
makes risk of HIV transmission higher. Approximately 20% of the 1.2 million people
living with HIV do not receive treatment, participate in intervention strategies, or know
their HIV/AIDS status Noor et al. (2013). The authors concluded the CDC should

33
implement HIV screening, which may not be enough to change the person’s sexual
behavior from unprotected to protective preventions.
In addition to the risks mentioned, men who have sex with men and women
continue to challenge health educators and counselors in regards to engaging this group
in open discussions about HIV risks. Saleh, Operario, Smith, Arnold, and Kegeles (2011)
conducted qualitative research in Northern California with 21 participants who were
African American adults. The study consisted of focus group discussions about HIV risks
and perceptions of HIV prevention services as well as the challenges and experiences of
African Americans.
Saleh et al. (2011) posited that in order to maximize privacy and honesty,
participants should be given choices about male or female counselors or educators. In
addition, HIV prevention services should be provided individualized feedback to
participants versus group discussions. The findings suggested that Black men health
programs may be a subtle approach to collaborate with social networks and encourage
church leaders and other community members to get involved in the fight against
HIV/AIDS.
Logan et al. (2013) conducted a community-based cross-sectional pilot study of
young homeless adults in the Portland, Oregon, metropolitan area in 2010. Participants
were between the ages of 18 and 25 years old. Many of the young people identified as
bisexual, gay, lesbian or transgender. Homeless communities require several types of
health care due to high levels of substance abuse, and exchange of sex for drugs, money
or housing. Over 50% of the participants reported discussing risks of HIV infection and

34
STI in personal relationships prior to sexual encounters. The study has at least one
limitation, such as the results may not be generalisable to other homeless youth that did
not receive risk behavior awareness training services. The study is significant because it
adds to the literature about HIV educational forums providing preventive messages
designed specifically for African American adults.
African American Identity and HIV/AIDS
Researchers studying the effects of HIV/AIDS on African American communities
have argued that knowledge of behaviors and transmission associated with the spread of
HIV has been linked with close romantic relationships, and individuals relying on
perceived safety, primarily because they believe that they are in a monogamous
relationship, and can trust their partners (El-Bassel et al., 2009). El-Bassel et al. (2009)
posited that the HIV epidemic is driven by risk factors such as African Americans unique
experiences, cultural values, attitudes, beliefs, poverty, lack of HIV education, gender
inequality, substance abuse, and social norms. El-Bassel et al. (2009) posited that African
American women empowerment strategies to challenge gender inequalities in regular and
casual relationships can incorporate specific messages to increase the person’s comfort
level when negotiating condom use may help to reduce risky sexual behaviors.
Drayton and Prins (2011) defined identity as a person’s characteristics that
indicate values, social norms, and beliefs of individuals from a social group. Identities are
framed by experiences from one’s past and present, which change the person’s
aspirations of how they interact with others. Drayton and Prins found that African
American identities are determined by environment social and cultural theories as well as

35
the person’s experiences. For example, negative identities are framed when people view
themselves as lazy, poorly motivated or less intelligent than other ethnic groups. On the
other hand, positive identities refer to one’s confidence in an ability to reach desired
goals.
Scottham and Smalls (2009) explored the extent to which attitudes and beliefs are
frequently emphasized through messages regarding specific behaviors. For example,
caregivers may communicate positive or negative messages to family members about
feelings of racial pride or racial barriers toward the African American group. A 3-year
longitudinal study was conducted to examine racial identity as it relates to African-
American female caregivers socialization with family members. Participants in the study
were 208 African American female caregivers whose children attended middle and high
schools in the Michigan Southeastern school district. The study was limited because
adolescent perspectives were not considered and the research was not generalizable to
male caregivers. The study was significant because it added to the literature about
African-American identities and change in behaviors.
Moreover, Baumgartner and Niemi (2013) posited that people have other
identities. According to Baumgartner and Niemi, sexuality and relationships are affected
after a diagnosis of HIV/AIDS. On occasions, people are stigmatized by negative social
identities, which involve work or spiritual identity. Culturally sensitive education can
remove fear associated with how the disease is acquired for people living in poor
neighborhoods.

36
By contrast, Higgins, Hoffman, and Dworkin, (2010) suggested men in
relationships use sexual power over African American women and are not agents of HIV
prevention. Despite the fact that some heterosexual men do not like condoms, lack of safe
sex practices makes women vulnerable to HIV/AIDS. In the context of this study,
Higgins et al., explored whether interventions specific to the uniqueness of African
Americans should include individualized assessment of possible stressors such as
childhood sexual abuse, and substance abuse. The authors concluded that couple-based
HIV prevention interventions such as attending training sessions together may increase
communication and express a desire to protect each other.
As the HIV epidemic continues to grow extensive cultural dialogue has increased
awareness about HIV (Kern & Foreman, 2013). Kern and Foreman (2013) posited that
essentially, African American male and female relationships are aggravated by an
imbalance of power between the sexes. The data obtained in this study revealed that
AIDS education prevention strategies to assist African American women in developing
safer sex behaviors against the spread of HIV may not be particularly cultural and gender
specific.
Equally important, Chajarich and Kow (2010) argued that gender is significant
among women and men. For example, both male and female behaviors affect one
another; their changing gender inequalities may highlight issues that men endure.
Education is needed to reduce HIV infection; however it should be gender neutral. The
research study is significant because it adds to the literature about how gender affects the
HIV infection epidemic.

37
In contrast to Chajarich and Kow (2010), O’Bryne (2012) argued that HIV testing
is important in preventing HIV infection. Consequently, HIV prevention methods should
include individuals most affected by the infection. It is alarming to learn that 25% of
Americans do not know their HIV status, but may be living with HIV (O’Byrne, 2012).
To the context of the 54-70 % new cases of HIV in the United States, it is suspected that
these are the people who are unaware of their HIV status. When a person receives a HIV
negative test result, it may confirm that either the person is in a monogamous relationship
or believe they are immune to the communicable disease (O’Bryne, 2012).
Furthermore, Holloway et al. (2012) argued that 35 to 50 House and Ball
communities in Los Angeles consisted of African Americans and Latino young adults
who did not live together, but attend social activities together such as dances and athletic
events. A mixed method study was conducted. Participants were concerned with HIV
prevention, but requested a more holistic approach such as job training, substance use and
harm reduction approaches as well as house placements. Participants at the House and
Ball events did not accept the HIV prevention messages. The majority of the community
had been tested for HIV and sexually transmitted infection (STI).
The study was limited in the context of data collection from participants who
lived outside of the House and Ball community, which made the data not representative
of all members of the House and Ball community. The self reports may have yielded
under- or over-reporting, which introduced bias. This study was significant because it
increases one’s understanding of barriers to HIV testing in the House and Ball
community (Holloway et al. 2012).

38
According to Wang and Arpan (2008), radio, television and magazines are
currently providing HIV prevention messages to the African American communities.
Ethnic identity characteristic are predictors of responses to HIV prevention messages.
The study found that expertise interventionists were more effective than non-expert
interventionists in facilitating behavioral changes in the same race and gender roles. The
study is significant because it provides insight into HIV prevention messages and
campaigns, in terms of racial and ethnic spoke persons for African Americans.
By contrast, Bond et al. (2009) posited that African American men who have sex
with men and women (men on the down-low) are highly associated with HIV risk
behaviors. The study found that men on the down-low reported they identified as being
homosexual or bisexual rather than heterosexual. The study results were limited in terms
of not being representative of African American men who have sex with men (MSM).
Equally important, Lopaz, Antoni, Fekete and Peneds (2012) conducted a cross-
sectional research study from 1998 through 2004 to examine biological and
psychological variables of women living with HIV. African American women between
the ages of 25 and 34 from low socio-economic status may have stressors that negatively
influence their health and well-being. However, a strong ethnic identity may provide a
person with a better overall quality of life by reducing depressive episodes as well as
provide a feeling of less perceived discrimination.
Although African American women living with HIV, with greater coping skills
have limited access to social support networks, comparatively, African American men
reported a perception of less race-related stress because of strong ties to their ethnic

39
identity (Lopaz, Antoni, Fekete, & Peneds, 2012). The sample size for the study included
92 African American women who were HIV positive. The study is significant because it
suggested that African American women with chronic medical conditions such as HIV
can access tailored cultural environmental resources to increase quality of life.
In like manner, Mackenzie et al. (2012) conducted in-depth post-intervention
interviews in Baltimore, Miami, New York, and San Francisco during 2005 with 68 HIV-
positive injection drug users. Peer-based interventions provided health-promoting
messages to reduce injection drug use practices and increase condom use during sexual
encounters. HIV prevention education provided by one’s own peers may be perceived as
trustworthy and knowledgeable about ways to end the spread of HIV.
In the social context of HIV prevention, peer mentoring affected a person’s social
identity and acceptance of HIV status. In addition, peer mentors provided a supportive
environment for individuals to communicate disclosure of HIV status and implement
positive social change. The findings in the study is significant because it supports the
need to find ways to curb the spread of HIV on an individual and peer level among
African-American adult communities (Mackenzie et al., 2012).
By contrast, Sengupta, Banks, Jonas, Miles and Smith (2011) examined the extent
to which HIV/AIDS stigma exists in situations in which individuals have received HIV-
related interventions. The study consisted of reviewing 19 studies related to HIV
interventions to reduce stigma. The finding in the study suggested that there are gaps in
the literature related to evidenced-based interventions designed to reduce HIV/AIDS

40
stigma. Of the 19 studies only two were recommended for replication because of being
deemed of higher quality.
Liu, Canada, Shi and Corrigan (2012) conducted a mixed-method research study
across cultures with participants from Chicago, Beijing, and Hong Kong regarding
employers’ attitudes toward hiring individuals with HIV. The study examined
employment stigma from several cultures. The findings in the study showed that
employers perceived HIV transmission from hiring HIV positive individuals as not being
competent to re-enter the job market. The study is significant because it contributed to the
literature regarding interventions tailored at reducing stigma related to hiring practices.
Radcliffe et al. (2010) posited that HIV positive men who have sex with men
experience multiple forms of stigma, such as sexual minority stigma, which includes
social avoidance. Individuals who experience shame over their HIV/AIDS status are at
higher risk of engaging in unprotected sex. Radcliffe et al. (2010) conducted a study with
40 African-American men between the ages of 16-24 years old who attended an
outpatient HIV clinic. The study had at least one limitation: the findings were not
generalizable to all African American young adults. However, HIV stigma interventions
that target young adults’ feelings are essential in HIV prevention.
Additionally, Gavin, Davis, Banks and Bing (2008) conducted a cross-sectional
research study with a convenience sample of 283 HIV positive African Americans to
explore how HIV-related stigma that negatively impacts African Americans, in areas
such as anxiety. The findings suggested that social support from one’s family and friends

41
is positively associated with perceived HIV-related stigma as well as major depression
and alcohol dependence.
Barriers to Preventing HIV/AIDS Transmission
Numerous issues associated with HIV/AIDS impact the African American
communities in general, such as stigma, and prejudice, and in many cases, extreme
poverty. Jacobson (2011) and Kuehn (2008) argued that older adults are sexually active,
however many Americans are unaware of this. Because older adults are sexually active,
susceptibility to HIV infection is greater than younger adults. For example, older adults
tend to have lower immune systems, which could shorten the HIV incubation period from
7.3 years for persons under age 50 to 5.7 years for older adults (Kuehn, 2008).
In addition, older adults may be at risk of HIV because of a decrease in using
condoms, which emphasizes the need for different HIV prevention strategies for different
age groups. Jacobson (2011) explained that many doctors are likely to stereotype older
persons over 50 years old by not discussing sexual health, which could delay HIV
diagnoses. On the other hand, older adults may be embarrassed to have open dialogue
with their doctors about sexual health concerns. Jacobson (2011) and Kuhn (2008) made
it clear that HIV/AIDS education designed to increase knowledge as well as discuss
methods of protection for older adults should be community based.
According to Jarlais, McCarty, Vega, and Bramson (2013), HIV is also prevalent
among those who inject drugs and share needles. In addition to sharing drugs and
needles, persons engaging in this situation may participate in unprotected sexual
encounters. Bowen (2012) and Jarlais et al. posited that many persons think that to

42
eliminate disparities in all ethnic groups, heterosexuals, men who have sex with men
(MSM), interventions may include exchange of syringes, over-the-counter pharmacy
sales as well as treatment for heroin use.
In the context of the Holt et al. (2012) study, ethnic MSM mistrust health
institutions more than other groups about the origin, prevention and treatment of
HIV/AIDS, and do not believe that their best interests are taken into account. Therefore,
fostering negative attitudes about health institutions in many cases may be a moderator of
unprotected sexual activities (Holt et al., 2012, p. 270). The Holt et al. (2012)
longitudinal study took place in Arizona, in which 394 MSM participants were identified
as gay, two spirited, or bisexual. The study examined the relationship between conspiracy
beliefs, discrimination, organizational suspicion, and institutional mistrust. Results
showed mistrust was higher among ethnic groups than Whites. The findings suggested
that mistrust is reduced when HIV prevention in local communities is conducted by
minority workers, and where prevention efforts are culturally appropriate.
Finlayson et al. (2011) posited that HIV infections in certain groups of people will
continue to increase in the United States if coordinated responses are not addressed (p. 2).
Research was conducted in metropolitan cities throughout the United States in 2008. Data
were collected via survey interviews to determine if MSM reported having unprotected
sex with casual and main partners, consumed alcohol or illegal drugs, or were diagnosed
with a sexual transmitted disease (STD), received HIV testing, or received behavioral
interventions. The study was limited in several ways. For example, the sampling selection
only considered participants who attended venues such as bars.

43
In addition, the participants may have under or over reported socially undesirable
behaviors such as not using condoms during sexual encounters or drug use.
The findings of the study suggested that effective evidence-based HIV prevention
approaches should be used in those communities where HIV is heavily concentrated if a
25% reduction in new HIV infections optimized (Finlayson et al., 2011, p. 10). The
findings further suggested that HIV status should be further explored in order to clearly
understand how MSM continue to transmit HIV to casual and main partners.
Crepaz et al. (2009) examined 37 studies of low income and unemployed
participants that showed African American females lacked negotiation skills related to
condom use because of a power imbalance in relationships. Many African American
females are dependent upon males for financial assistance. The study also showed that
gender-specific and cultural components as well as skills building in negotiating safe sex
practice training related to correct condom use should be delivered by women. The
training would be significant in terms of successful HIV reduction.
African American Culture and Spirituality
Culture is important to African Americans (Martin et al., 2010). Martin et al.
(2010) explored “the influence of culture and discrimination on care seeking behaviors of
elderly African American” in the South (p. 311). A qualitative phenomenology study was
conducted with 15 African American participants. In-depth interviews were conducted
and indicated that several themes emerged such as distrust of doctors, race of doctors and
the importance of spirituality on health issues. The study was limited due to the fact that
generalizations could not be made. However, the findings may suggest that African

44
Americans religious and spiritual beliefs continue to guide their health care practices
(Martin et al., 2010, p. 323).
Similarly, Taylor, Chatters and Arbor (2010) conducted a study to examine the
importance of spirituality and religion in the lives of African Americans, Black
Caribbean Blacks and non-Hispanic Whites. A total of 6,082 persons participated in face-
to-face interviews in the participant’s homes. Participants were 18 years old and older.
The findings showed that African Americans and Caribbean Blacks had similar high
levels of religiosity and spirituality than non-Hispanic Whites. The findings suggest that
African American’s religion assessments have practical implications for some levels of
educational settings such as church-based social networks and supports related to
intervention programs (Taylor, Chatters & Arbor, 2010, p. 289).
According to Hamlet (2011), African American church services are maintaining
cultural expression traditions through call-and-response communications between
preachers and congregants. Similarly, Gilbert, Harvey, and Belgrave (2009) argued that
African Americans have a set of principles that assist them in addressing social problems.
For example, the principles include creativity and faith in the African American struggle
against discrimination as well as group stigma, family unity, and community unity.
Gilbert et al. (2009) found that when the principles are incorporated into African
American interventions, behavior change and community empowerment is reaffirmed,
which has implications for engaging in HIV prevention.

45
AIDS-Related Stigma
Although community involvement and collaboration can shape African American
adults’ knowledge, attitudes, beliefs and sexual behaviors, AIDS-related stigma has been
discussed recently, and has been a barrier to providing culturally, and sensitive
HIV/AIDS prevention programs. Kern and Forman (2013) conducted research in New
York State to examine outdoor campaigns related to Contemporary Public health AIDS
and HIV advertisements in subway trains and stations that were placed at pedestrian’s
eye levels. The advertisement (ads) messages used key words, such as “We’re Still Here”
and “It’s Never Just HIV” (Kern & Forman, 2013, p. 1149). Kern and Forman (2013)
also examined each prevention campaign run time, target audience, funding, placement of
public venue as well as the overall messages of HIV prevention. The messaged focused
on gay men, MSM, Hispanics (under 40 years old), and African Americans because these
groups accounted for more than half (57%) of the new diagnoses in New York State. The
findings of the study revealed the ads included scare tactics that added to stigma about
HIV/AIDS in reference to reinforcing past ideologies that HIV is a gay disease, however,
effective messages included the need to take personal responsibility (Noar, Palmgreen,
Chabot, Dobransky, & Zimmerman, 2009).
Uhrig, Bann, Wasserman, Guenther-Gray, and Eroglu (2010) posited that
effective campaigns are enhanced by formative evaluations of the specific messages that
guide the development of sophisticated strategies. The study provided insight into the
types of ad campaigns that show specific ethnic groups account for a high number of HIV
cases in the United States. Efforts to reduce race and ethnicity health disparities may wish

46
to consider these outcomes (Uhrig, Bann, Wasserman, Guenther-Gray, & Eroglu, 2010).
Ethnic differences and stigma are well documented as it relates to HIV/AIDS prevention.
Generally, stigma is created when people pass judgment upon members of a group that
goes against social norms (O’Brian, Bayoumi, Davis, Young, & Strike, 2009; Pace,
2011).
According to Grov et al. (2013), HIV-related stigma can lead to reluctance to
disclose HIV status. Many Christian leaders advocate abstinence, but some religious
communities targeting HIV/AIDS endorse the mainstream global HIV prevention
strategies. Grov et al. posited that HIV-status stigma comes from a lack of understanding
about HIV transmission, and men’s mistrust about receiving inaccurate responses from
possible online partners.
Similarly, Zamboni, Robinson, and Bockting (2011) argued that theories of HIV
prevention can help to explain certain aspects of risk-taking behavior that occurs in a
targeted population and can be useful as a framework for the goals of HIV/AIDS
prevention (Coleman, Lindley, Annang, Saunders, & Gaddist, 2012) disclosing one’s
HIV status can decrease psychological isolation, stress and depression.
Theories of Intervention
Intervention programs are typically needs driven. Successful interventions
require a change in behavior. Many interventions that focus on communication, beliefs,
knowledge and the integration of theory combined with skills building provide
opportunities for healthy life changes (Frye et al., 2012). A pilot study conducted by Frye
et al. (2012) took place in New York City prior to developing a theory-based HIV/AIDS

47
group behavioral intervention titled, “Straight Talk” for African American heterosexual
men who lived in the high prevalent, poor minority neighborhoods. The Frye et al. (2012)
study integrated the rational choice theory, which posited that protected sexual practices
are influenced by the individual’s attitudes and social norms, environmental factors such
as poverty, incarceration, and lack of education attainment and behavioral control.
While the study indicated that HIV behavior interventions have been shown to be
effective in terms of increased condom use, it did not include heterosexual women
neglecting the problematic issues associated with negotiating condom use within casual
relationships. The findings in the study also suggested that African American
heterosexual men have the opportunity to adopt new safe sexual practices, as well as
increase their knowledge and skills about HIV prevention. The theory of planned
behavior provided specific insight into what may shape the community member’s
attitudes, subjective norms, perceived behavioral control, intentions and
sociodemographics about positive sexual behavioral practices, and how problems can be
solved through church assessments and community involvement as well as collaboration.
One approach to understanding high risk behaviors related to HIV is to examine the
psychosocial antecedents of condom use, to develop effective theory driven HIV/AIDS
training programs, and to learn more about people’s motivation to initiate participation in
safe sex practices and maintain healthy behavior (Frye et al. 2012).
Research on the theory of reason action/theory of planned behavior has
dominated this field of study. However, this model relied heavily on self-reports to
measure behaviors, which can present memory bias. As a result, a baseline measurement

48
was done to measure the participant’s intentions to change high-risk sexual behavior. The
individual’s attitudes, subjective norms, perceived behavioral control, socio-
demographics about HIV, and the effects of the virus, can profoundly impact intentions
to change behaviors, and the likelihood that the person will take the most appropriate
action to prevent the illness (Ajzen, 2011).
More specifically, the attitudes, beliefs, and intentions have been significantly
associated with the HIV risk behaviors in some populations (Ajzen, 2011). The TpB can
be incorporated into specific educational programs and community settings in concrete
ways. For example, the training varies depending upon the specific focus and audience.
The TpB can be used to establish a foundation for the education program as well. The
conclusions arising from this study served to address behaviors conducive to HIV/AIDS
that are believed to be generalizable among the adult community. Public health efforts
can potentially improve human and social conditions for this population by reducing the
incidence of widespread health problems and multiple secondary effects, which may lead
to the individual’s physical impairment or death.
Summary
HIV/AIDS can be prevented by understanding the attitudes, subjective norms, and
perceived behavioral control of a population by which the disease is acquired. A review
of the literature revealed that, even though adults were knowledgeable about HIV/AIDS,
their sexual risk behavior varies based on their ethnicity and cultural values. The Theory
of Planned Behavior (TPB) described the behavior of an individual with no control over
the behavior because of external influences. Ajzen (2011) mentioned that human action is

49
guided by: (a) a person’s behavioral beliefs or attitudes, which are the belief and
evaluation of the outcomes (decision to engage in safe sex or not engage); (b) normative
beliefs, which are others expectations and the person’s motivation to comply with the
particular expectations or subjective norm; (c) the person’s control beliefs, which are
factors that allows easy or difficult performance in the particular behavior, or (d)
perceived behavior control, which is acceptance of behavior. In other words, a particular
behavior may be engaged depending on the adult’s expected acceptance of their peers.
Additionally, the literature search identified numerous scholarly peer-review
research articles to suggest that the identified population is starting to engage in
significant dialogue with church leaders about HIV/AIDS transmission (Doody &
Noonan, 2013). Social change can be realized by working with the community leaders to
develop and implement church-based HIV/AIDS program training that will provide
knowledge and skills to participate in the fight against the infection and disease
(VanDevanter et al., 2011).
In the context of implementing church-based HIV/AIDS prevention training,
community health advocates collaborated with church leaders to plan and implement
annual health care revival meetings, to participate in screening activities, and
dissemination of health information that was integrated with inspirational singing and
scripture readings. This strategy incorporated a holistic approach, which emphasized the
importance of integrating the spirit, the body, and the mind in efforts to improve the
community’s health (Parrill & Kennedy, 2011). Spreading the word to the community
and decision makers about ways to protect and promote health may prove challenging but

50
necessary (Parrill & Kennedy, 2011). The degree and commitment to fight HIV/AIDS
have increased substantially in recent years because of effective leaders in the
community.
The church can be a responsible advocate in fighting against HIV/AIDS by
developing culturally appropriate educational materials, and thus effect social change.
The proposed study filled one gap in the literature by adding to the body of knowledge
that church leaders and program planners can develop specific church-based HIV/AIDS
prevention interventions suited for adults living in similar demographic areas that can
help in developing educational interventions to reduce the risk of infection by gaining
insight about the importance of attitudes, subjective norms, perceived behavioral control,
and intentions relative to changing sexual risk behavior.
This chapter provided a picture of the literature on HIV/AIDS as it pertains to
members of African American churches in the metropolitan South, the literature on the
effects of attitudes, subjective norms, perceived behavioral control, and intention on
behavior, and role of churches in HIV/AIDS education. The next chapter will address the
methodological approach chosen to answer the research questions.

51
Chapter 3: Research Method
Introduction
The purpose of this quantitative cross-sectional study was to establish and
compare attitudes, subjective norms, perceived behavioral control, and intentions to
engage in safe sex practices, comparing two Christian church congregations, one with a
HIV/AIDS prevention program and one without. This study’s results may inform future
public health practices and policies that will promote effective HIV interventions based
on specific cultural and behavioral patterns. In Chapter 3, I address the research design
and data collection methods and cover the research design/rationale, research
methodology, questions, hypotheses, access to participants, participant selection and
sample, ethical protection measures, instrumentation, data collection, role of researcher,
and methods of data analysis as well as issues of reliability and validity.
Research Design and Rationale
A cross-sectional design was chosen to survey adults of two Christian churches in
a metropolitan area in a city in the South on the topic of HIV/AIDS prevention. The cross
sectional design was chosen because data were collected within a short time frame. The
use of a survey provided a snapshot of the variables included in the study at one
particular point in time. Additionally, the advantages of using a cross sectional approach
to this study included the generation of data on many variables such as attitudes and
behaviors and the generation of hypotheses for future research. The disadvantages
included that causal relationships cannot be inferred, the sample size requirements were
large, and generalizability is limited.

52
Participants completed a confidential and anonymous questionnaire to elicit
information about the independent variable of exposure of church-based HIV/AIDS
prevention program and dependent variables of attitude, subjective norm, perceived
behavioral control, and intention to engage in safe sexual practices to prevent HIV/AIDS.
The covariates included age, gender, church status, marital status, education attainment,
and income. All items in the questionnaire were chosen because of their direct bearing on
the two research questions, and each separate section of the questionnaire directly
addressed one of these two questions.
The research approach and design for the study sought to answer the questions
about how adults attending churches perceive the risks and consequences of HIV/AIDS,
how their actual sexual behavior places them at risk for HIV/AIDS, and how they
perceived their control over decisions about sexual risk behavior. Although HIV/AIDS
and adult church members have been studied with a growing incidence of HIV/AIDS, in
particular among adults, research within the adult age group has not been conducted.
Setting and Sample
The setting for the survey participation was either in a private room in church, the
participant’s home, or other private setting of their choice in this Southern city. To
minimize contact with participants, the TPB questionnaire was distributed to both
churches and placed in a vertical locked mailbox outside of the church offices. The two
church congregations were selected for the study because one provided a HIV/AIDS
prevention program and one did not. The church that did not provide HIV/AIDS
prevention may not have yet been exposed to information acquired in the prevention

53
program that could enhance their knowledge and influence their perceptions of risks
associated with HIV/AIDS. A total of approximately 200 active adults (100 plus
participants from each church) attended the selected churches in 2014. Using the Creative
Research Systems (2013) with an alpha of .05 and a power of 95, a sample of 132
individuals participates was needed in order to have a statistically viable sample of the
total population.
The criteria for inclusion in the study were as follows:
1. Participant was a church congregant who received church-based HIV/AIDS
prevention via a program in 2009.
2. Participant was a church congregant who did not receive church-based
HIV/AIDS prevention via a program in 2009.
3. Participant identified him or herself as either 18 years of age or older
4. Participant was able to read and write English.
The exclusion criteria were as follows:
1. Participant was not 18 years old or older.
2. Participant was not able to read or write English.
Research Methodology
A research study design was based on the research questions, the sample size,
ethical measures for participants, the budget, and the amount of time that was necessary
to completethe steps in the process. A descriptive quantitative cross-sectional research
design was selected for this study to focus on the individual cases of participants at one
particular point in time. The study’s goal was to establish and compare attitudes,

54
subjective norms, perceived behavioral control, intentions, and sexual risk behavioral
practices of adults from two church groups as measured by age, gender, marriage status,
education attainment, and income via a TPB questionnaire.
In addition, the study determined the relationship between the independent
variable (exposure to the church-based HIV/AIDS prevention program) and the
dependent variables, which included attitudes, subjective norms, perceived behavioral
control, and intentions. The study was designed to compare the statistical differences in
responses between individuals in both church groups.
Population
The target population was adults 18 years of age or older who are members of the
congregation or attended the two selected churches. The participants identified
themselves as 18 years old or older and able to read and write English.
Sampling and Sampling Procedures
The sampling strategy was based on a convenience sample of adult participants
attending a church that had provided an innovative HIV/AIDS prevention program, and a
traditional church that did not provide HIV/AIDS training to their congregation.
Additionally, participants provided their age range to confirm that they were between the
ages of 18 or older living in a region in the community. According to Creative Research
Systems (2012), the sample size calculator indicated ensuring a confidence level of 95%
and confidence interval of 5, as well as an approximate population of 100 people in each
church. The sample size for this study (n = 132) was required to measure attitudes,
subjective norms, perceived behavioral control, and intentions relative to sexual

55
behaviors regarding HIV/AIDS prevention responsibilities. As a result, the sample size
was 64 participants from one church and 68 from the other.
Recruitment of Participants
Arrangements were made with church leaders to recruit participants through
church service announcements, flyers, and invitation letters. Participants were informed
that the TPB questionnaires should be completed in their home or other private
environment of their choice. The study’s contact flyer (see Appendix B) with information
about the aim of the study, the risks, and benefits as well as how the information was
collected was provided to both sets of church officials. Additionally, information on the
flyer was included with a statement that participants who agree to complete the TPB
questionnaire were implying informed consent, and all information obtained would be
kept confidential (see Appendix D).
Ethical Protection Measures
Adult participation in the study was strictly voluntary (Terrell, 2012). To protect
anonymity and privacy, the questionnaire was distributed to each church. Time was
allowed for participants to complete the questionnaire in a setting of their choosing and
then to return it in a sealed envelope to a locked vertical mailbox outside each church
office, which was a location that was accessible but fairly private. During the
introduction to the study, it was explained to participants that their identity and integrity
of their answers would be protected, via my exclusive access to the documents.
Participants’ confidentiality was protected—neither their names nor their signatures were
requested on the survey document.

56
All participants were assured that they were free to withdraw from the study at
any time, without fear of reprisal, to protect them from any associated stress during the
process of completing the questionnaire. In addition, it was made clear to all participants
that if they decided to withdraw from the study after receiving the questionnaire, they did
not have to return the survey because that particular questionnaire would be eliminated
from the sample.
Although this research study posed no risks to the adult participants, some may
have felt uncomfortable answering sensitive questions regarding sexual activities. Adult
participants were informed that they would not receive any personal compensation for
their participation in the study, and they would not give up any legal rights. Additionally,
Walden University’s Institutional Review Board approval was granted prior to data
collection. Walden’s approval number for this study was 05-09-14-0097025.
Instrumentation
The TPB is a general type of survey instrument that was modified to address safe
sex practices (see Appendices E and F). The TPB survey was comprised of 13 questions
designed to measure adults’ attitudes towards using safe sex practices, the subjective
norm, perceived behavioral control, and the intention about the behavioral outcomes,
such as engaging in safe sex practices or not using condoms or dental dams during sexual
relations.
Consequently, the TPB questionnaires were distributed to each church group to
minimize contact with the participants as they received, filled out, and returned the

57
instrument. Another major advantage of quantitative research is that it allowed one to
generalize one’s findings beyond the participant group (Bernard, 2013; Creswell, 2013).
Data Collection
Data were collected using the adapted items from the TPB survey instrument, a
guide to predicting specific intentional behavior. In addition, the TPB responses to
questions were measured on a 7-point Likert scale. The TPB survey instrument asked
questions about the participants’ intentions to use condoms during sexual relations,
attitudes toward the behavior, subject norm (beliefs), and perceived behavioral control.
Each questionnaire was assigned a unique identification code to be used for organization
and data analysis
Role of Researcher
The role of the researcher in the quantitative cross-sectional phase of this research
study involved distributing the TPB survey instrument in a sealed envelope to two
different church groups of participants. The questionnaires were distributed to each
church, and participants were expected to complete it in a private setting of their
choosing and return it in a sealed envelope to a locked mailbox at each church, thereby
maintaining confidentiality. The standardized methods incorporated the use of a
convenience sample selection, with reliability and validity checks of the survey
instrument. Rigorous statistical analysis techniques were used to analyze the collected
data. Finally, the data results were interpreted using the statistical significance of
established functions and values.

58
Operationalization of Variables
Direct measures of attitude, subjective norm, and perceived behavioral control are
sufficient to predict intention and behavior; however, if effective behavior change
interventions are studied, then behavioral, normative, and control beliefs must be
assessed (Ajzen, 2011). The TPB questionnaire addressed the variables of attitude,
subjective norm, perceived behavior control, and intention of adults who have been
exposed to a church-based HIV/AIDS prevention program and those who have not, with
a four-section instrument corresponding to each of the variables as follows:
Section A: Attitudes
Attitudes are consistent favorable or unfavorable responses to a stimulus
(Altmann, 2008). Four questions in this section were adapted to the cultural realities of
the adult church population. The variable/scale score was calculated using a Likert scale
of 1 to 7. The higher the attitude scores, the more positive the responses (see Table 2).
Attitude scores towards condom use or dental dam use is being measured for individuals
who have participated in a church-based HIV/AIDS prevention program and those who
have not.

59
Table 2
Variable Related to Attitude
Survey Question 1: Having sex with only one partner (a monogamous relationship), is:
ineffective: 1: 2: 3: 4: 5: 6: 7: effective
Survey Question 2: Buying a condom or dental dam (a latex covering used to prevent
exchange of bodily fluids), is:
ineffective: 1: 2: 3: 4: 5: 6: 7: effective
Survey Question 3: Using or asking a partner to use a condom or dental dam, is
ineffective: 1: 2: 3: 4: 5: 6: 7: effective
Survey Question 4: A partner’s sexual history will influence my decision to engage in
sexual activity with them, I:
strongly disagree 1: 2: 3: 4: 5: 6: 7: strongly agree
Section B: Subjective Norm
Subjective norm refers to perceived social pressure (Ajzen, 2011). Three
questions in this section were adapted to suit the adult church population. The
variable/scale score was calculated using a Likert scale of 1 to 7. The higher the
subjective norm scores, the more positive the responses (see Table 3). Subjective norm
scores towards condom use or dental dam use as the result of social pressure from family
and friends was measured for individuals who have participated in a church-based
HIV/AIDS prevention program and those who have not.

60
Table 3
Variable Related to Subjective Norm
Survey Question 1: Most people who are important to me think that:
I should not: 1: 2: 3: 4: 5: 6: 7: I should
use a condom or dental dam during sexual relations with casual or regular partners each
time in the forthcoming month.
Study Question 2: It is expected of me that I use a condom or dental dam during sexual
relations with casual or regular partners each day in the forthcoming month, it is:
extremely unlikely: 1: 2: 3: 4: 5: 6: 7_: extremely likely
Study Question 3: The people in my life whose opinions I value would:
disapprove: 1:_2:_3: 4:_5: 6: 7: approve
of my using a condom or dental dam during sexual relations with casual or regular
partners each time in the forthcoming month.
Section C: Perceived Behavioral Control
Perceived behavioral control refers to an individual’s perception of his or her
ability to perform a specific behavior (Ajzen, 2011). Perceived behavioral control was
measured by four questions inquiring about a person's confidence in whether he or she
was capable of performing a specific behavior. Degrees of perceived control were
measured by whether an individual affirms that he or she was in control of a behavior or
that factors beyond his or her control determined behavior. A Likert scale from 1 to 7
indicated the degree to which the respondent agreed or disagreed with each statement,

61
with 1 as strongly disagree and 7 as strongly agree (see Appendix E). (see the perveived
behavior control variable below in Table 4)
Table 4
Variable Related to Perceived Behavioral Control
Study Question 1: Most people who are important to me think that:
I should not: 1: 2:_3:_4:_5: 6: 7: I should
use a condom or dental dam during sexual relations with casual or regular partners each
time in the forthcoming month.
Study Question 2: It is expected of me that I use a condom or dental dam during sexual
relations with casual or regular partners each day in the forthcoming month, it is:
extremely unlikely: 1: 2:_3:_4: 5:_6: 7: extremely likely
Study Question 3: The people in my life whose opinions I value would:
disapprove: 1: 2: 3: 4: 5:_6:_7: approve
of my using a condom or dental dam during sexual relations with casual or regular
partners each time in the forthcoming month.
Study Question 4. It is mostly up to me whether or not I use a condom or dental dam
during sexual relations each time in the forthcoming month:
strongly disagree: 1: 2:_3: 4:_5:_6:_7 _: strongly agree
Section D: Intention
Intention refers to a person's motivation to perform a specific behavior (Ajzen,
2011). An intention was based on attitude, subjective norm, and perceived behavioral
control toward the behavior and usually precede behavior. Intention was measured by
two questions inquiring about a person's intention to use condoms or dental dams. The

62
questions for perceived behavioral control, subjective norm and intention were
constructed by the researcher with the aid of guidelines developed by Ajzen (2011) for
TPB constructs. (see Table 5).
Table 5
Variable Related to Intention
Survey Question 1: I intend to use a condom or dental dam each day in the forthcoming
month
extremely unlikely: 1: 2: 3:4: 5: 6: 7: extremely likely
Survey Question 2: For me to use a condom or dental dam during sexual relations with
my casual or regular partners each time in the forthcoming month is:
harmful: 1: 2: 3: 4: 5: 6: 7: beneficial
unpleasant: 1: 2: 3: 4: 5: 6: 7: pleasant
bad: 1: 2: 3: 4: 5: 6: 7: good
worthless: 1: 2: 3: 4: 5: 6: 7: valuable
unenjoyable: 1: 2: 3: 4: 5: 6: 7: enjoyable
Instrumentation
The dependent variables such as attitudes, perceived behavioral control, and
intentions were the variables addressed in the study. The attitude section listed four
questions, the subjective norm section listed three questions, the perceived behavioral
control section listed four questions, and the intention section listed two questions. The
TpB survey instrument (see Appendix E) is comprised of 13 questions designed to
measure adult’s attitude towards using safe sex practices, the subjective norm, perceived
behavioral control, and the intention about the behavioral outcomes, such as engaging in
safe sex practices or not using condoms or dental dams during sexual relations. The

63
covariates included age, gender, marital status, church status, ethnicity, education
attainment, and household income (see Table 6) Participants were asked to circle the
appropriate answer for each item. For example, during the introduction to the survey,
participants were free to ask questions about any items relative to the clarity of a question
or statement (see Table 6).
Table 6
Covariates Related to Survey Questions
Survey Question 1: What is your gender?
Female Male
Survey Question 2: What is your age?
Survey Question 3: What is your church membership status?
Member Visitor
Survey Question 4: What is your current marital status?
never married divorced/separated
married single (in a committed relationship)
widowed single (not in a committed relationship)
Survey Question 5: What is your identity?
American Indian or Alaska Native
Asian
Black or African-American
Hispanic or Latino
Native Hawaiian or Other Pacific Islander
Some Other Race
White
(table continues)

64
Survey Question 6: What region of the city do you live in?
Northside Eastside Southside Westside
Survey Question 7: What education level have you achieved?
Less than 9th grade Associate Degree
Some High School, no diploma Bachelor's Degree
High School Graduate (or GED) Master's Degree
Some College, no degree Doctorate
Survey Question 8: What is your yearly household income?
Less than $15,000 $50,000-$75,000
$15,000-$24,999 $75,000-$99,999
$25,000-$49,990 $100,000-$149,999
$150,000-$249,000 More than $250,000
Methods of Data Analysis
In the quantitative cross-sectional study, Cronbach’s alpha was used to measure
internal reliability and test the multiple questions about each related concept such as
attitudes. The attitude, subjective norm, perceived behavior control and behavior
intention variables were measured by creating scales from the associated survey
questions. The original survey questions were measured on a 7-point Likert scale. After
entering the data each item was checked and rechecked to avoid any errors. Each item in
the survey was entered in an Excel spreadsheet and imported into the Statistical Package
for the Social Sciences (SPSS 21).
Before proceeding with the analysis, the data was confirmed as accurate and
complete. Missing data were handled by discarding two discrepant cases. Final analysis
was carried out on the remaining valid cases that remained.

65
Reliability and Validity
The survey instruments, pilot studies, and data reduction (Cronbach’s alpha) are
just a few of the methods usually reported in quantitative studies to judge if the
instrument was reliable. Cronbach’s alpha was measured on the data to determine internal
consistency and reliability. Face and content validity of the TpB (survey instrument) was
constructed based on adequate sample and coverage of participants being studied.
Threats to Validity
The potential threat of test reactivity in the measurement of identity was not a
cause for concern in this study because the questionnaire was anonymous and names
were not included. History was not a threat for the two groups for the comparison/control
design used in the study. Maturation is not a threat to the two-group design; however
sample selection may have been a threat because random sampling and random
assignment was not conducted, which could have caused the comparison groups to be
unequal. Mortality was a threat to the study because more than one group was being
studied and only one participant returned the survey in the sealed envelope unanswered,
which effected selection slightly and effects of selection may have existed. In addition,
another participant did not return the questionnaire to the locked mailbox as instructed.
More specifically, pilot testing or test-retest reliability showed the results of the
same survey instrument after being distributed and completed. This procedure allowed
me to compare, and correlate data to determine if words should be reworded, or deleted
from the survey instrument. Multiple items were used to measure the construct to
determine the reliability of measurement (Kimberlin & Winterstein, 2008). In addition,

66
the procedures utilized were documented to check and recheck data during the research
study process. The contextual data from two locations were compared to establish a
baseline understanding of the phenomenon with which subsequent research can be
compared. A trail of decision-making was presented regarding data collection and
analysis during the research process (Lewis, 2009). Equally important was Lewis’s
(2009) explanation that the chance of the research being replicated in another setting is
dependent upon the researcher’s bias, positions, central assumptions, and selection of
participants. Consequently, a comprehensive description of the study findings is
presented in the findings of Chapter 4.
Summary
Chapter 3 focused on data collection methods and analysis for a descriptive
quantitative cross-sectional research study. The ethical protection measures were
discussed for the participants to ensure they are treated with respect. More specifically,
specific protocols were described and completed to answer the research questions;
described how the protocols were completed, justified the selected research design, and
explained how the results were analyzed via statistical tests. Methods to ensure reliability,
and validity of the survey instrument were discussed. These methods of inquiry lead to
finding presented in Chapter 4 of the study.

67
Chapter 4: Results
Introduction
In this chapter, I address data collection and the statistical analysis of those data.
The data were generated by responses to the modified TPB questionnaire that was used to
assess HIV/AIDS prevention among adults in two Christian churches in a Southern city.
The TPB protocol was also used as the conceptual framework. The results of the pilot test
and the main study are detailed. Also covered in this chapter are the processes by which I
converted the data, statistically analyzed them, interpreted the results through the
conceptual framework, and tested the hypotheses based on the results of the Wilcoxon
Signed Ranks Test. The following two research questions were asked:
1. To what extent does exposure to church-based HIV/AIDS prevention
programs influence attitude, subjective norm, and perceived behavioral
control of adult church attendees in the South?
2. To what extent does exposure to church-based HIV/AIDS prevention
programs influence intention to engage in safe sex practices (condom or
dental dam use) of adult church attendees in the South?
The hypotheses and four null hypotheses were tested by relevant statistical
processes.
H01: There is no statistically significant difference between attitude scores towards
condom use or dental dam use for individuals who have participated in a church-based
HIV/AIDS prevention program and those who have not.

68
HA1: There is a statistically significant difference between attitude scores towards
condom use or dental dam for individuals who have participated in a church-based
HIV/AIDS prevention program and those who have not.
H02: There is no statistically significant difference between subjective norm scores
towards condom use or dental dam for individuals who have participated in a church-
based HIV/AIDS prevention program and those who have not.
HA2: There is a statistically significant difference between subjective norm scores
towards condom use or dental dam for individuals who have participated in a church-
based HIV/AIDS prevention program and those who have not.
H03: There is no statistically significant difference between perceived behavioral
scores towards condom use or dental dam for individuals who have participated in a
church-based HIV/AIDS prevention program and those who have not.
HA3: There is a statistically significant difference between perceived behavioral
scores towards condom use or dental dam for individuals who have participated in a
church-based HIV/AIDS prevention program and those who have not.
H04: There is no statistically significant difference between intention scores
towards condom use or dental dam for individuals who have participated in a church-
based HIV/AIDS prevention program and those who have not.

69
HA4: There is a statistically significant difference between intention scores towards
condom use or dental dam for individuals who have participated in a church-based
HIV/AIDS prevention program and those who have not.
Analyzing the Data
Pilot Test
The pilot test was conducted in May 2014 with 12 adult church attendees (six
from each church congregation). Only adults who fulfilled the eligibility criteria were
asked to participate in the pilot test. The purpose of the pilot test was to establish the face
validity of the TPB questionnaire that was used in the study. The study was introduced
during church services to inform possible participants about their choice to volunteer in
the study. The 12 participants were asked to indicate if the items were difficult to answer,
whether the questionnaire was too repetitive, too long, or if the wording was annoying.
Participants were allowed as much time as needed to read the informed consent
form and complete the questionnaire. The questionnaires were retrieved from each church
after a period of 1 week to allow sufficient time for participants to complete them. All 12
adults completed the pilot test questions, and there were no marks to indicate any of the
questions were difficult or hard to understand; therefore, I assumed that the questions
were clear (see Appendix D). The participants reported that the questions were clear to
them; however, to address their feedback that some questions were repetitive, a content
validity ratio (CVR) was performed on the questionnaire. The data collected and their
correspondence with the purposes of the study were evaluated quantitatively by Lawshe's
(1975) method. To apply Lawshe’s method, expert panels of six professionals were

70
assembled who were familiar with the subject and asked to evaluate all the questions on
the TPB questionnaire. The expert panel consisted of a physician, a pastor with a
doctorate, two Masters level nurses, and two Senior Services HIV staff members. The
experts on the panel were asked to indicate whether the questions were essential by
responding to whether they understood the instructions, the intent of the study, any
problems with the questions, and recommendations on how to improve the study, which
was necessary for the operationalization of the theoretical construct.
According to Lawshe (1975), the formula used to quantify the content validity is
as follows: content validity ratio (CVR) = (ne-N / 2) / N / 2 validated whether a question
was essential or not if more than half of the panel reviewers agree. The ne is the number
of panel reviewers (experts) who indicated the reagent was essential, while N is the total
number of panel reviewers who reviewed the question for this reagent. The CVR is
positive if more than half of the experts indicated that a particular question was essential
and negative when more than half of the experts indicated the questions were essential.
The CVR is zero when all of the experts indicated the quality of the question was
essential. The panel evaluation concluded that two of the original questions were related
but not essential to the operationalization of the TPB. The panel experts’
recommendations were consistent with feedback from participants in the pilot test. The
panel recommended a shorter version of the survey by maintaining the four questions in
Section A (Attitude), three questions in Section B (Subjective Norm), and four questions
in Section C (Perceived Behavioral Control), and reducing the number of questions from

71
four to two in Section D (Intention). The original survey can be found in Appendix D and
the modified TPB questionnaire in Appendix F.
Data Collection
The study was introduced to both churches in the third week of May 2014 by
announcing the opportunity to participate using the invitation letter, which included
information that participation was voluntary and informed consent was implied. The
questionnaires, Invitation Letter, and the Recruitment Flyer were enclosed in a sealed
envelope and distributed to both church groups. If participants agreed to be a part of the
study, the recruitment process began with when adults over the age 18 and above who
were able to read and write accepted the sealed envelope with the questionnaire,
invitation letter, and recruitment flyer inside. Participants were informed that there was
no monetary compensation being provided. Participants were also informed that the
information they provided was strictly confidential and did not require their names or any
other personal information. Participants were instructed that they could fill out the
questionnaires in their church office, home, car, or any other private area of their choice
and that it would take about 15 minutes to complete, and they were asked to return
surveys in 3 business days to a locked mailbox outside each church office. Some of the
participants preferred to return the questionnaires within 1 week rather than 3 business
days, so I agreed to allow them sufficient time to complete them in 1 week. The data
collection commenced on June 8, 2014 and was expected to continue until June 15, 2014;
however, 132 completed surveys were completed by the end of the day on June 8, 2014.
The experimental group included 68 respondents and the control group consisted of 64.

72
The contents of the locked mailbox were retrieved from each church group, and
then the analysis began. Data were manually entered into Excel spreadsheets, double-
checked for accuracy, and then imported into SPSS 21 for analysis. The survey included
eight demographic questions to determine the characteristics of the experimental and
control group were similar. Tables 7 and 8 present descriptive statistics for the groups.
Table 7
Experiment Group Sociodemographic Main Study
Variable
n
Percent
What is your gender?
Female 49 72.1
Male 19 27.9
What is your age range?
18-25 6 8.8
26-35 14 20.6
36-45 12 17.6
46-55 18 26.5
56-65 11 16.2
65+ 7 10.3
What is your church status?
Member 57 83.8
Visitor 11 16.2
What is your marital status?
Never married 8 11.8
Married 24 35.3
Widowed 4 5.9
Divorced/separated 13 19.1
Single in a committed relationship 9 13.2
Single (not in a committed relationship 10 14.7
(table continues)

73
Variable
n
Percent
What is your racial identity?
American Indian or Alaska Native 0 0.0
Asian 0 0.0
Black or African American 68 100
Hispanic or Latino 0 0.0
Native Hawaiian or Other Pacific Islander 0 0.0
Some Other Race 0 0.0
White 0 0.0
What region of the city do you live in?
Northside 21 30.9
Eastside 25 36.8
Southside 12 17.6
Westside 9 13.2
What level of education have you achieved to date?
Less than 9th grade 3 4.4
Some High School, no diploma 6 8.8
High School Graduate (or GED) 17 25.0
Some College, no degree 27 39.7
Associate Degree 6 8.8
Bachelor’s Degree 7 10.3
Master’s Degree 2 2.9
Doctorate 0 0.0
What is your yearly household income?
Less than $15,000 16 23.5
$15,000 - $24,999 14 20.6
$25,000 - $34,999 6 8.8
$35,000 - $49,999 16 23.5
$50,000 - $74,999 7 10.3
$75,000 - $99,999 4 5.9
$100,000- $149,999 3 4.4
$150,000- $249,999 2 2.9
More than $250,000 0 0.0
Note. n = 68.

74
Table 8
Control Group Sociodemographic Data Main Study
Variable
n
Percent
What is your gender?
Female 40 62.5
Male 24 37.5
What is your age range?
18-25 12 18.8
26-35 8 12.5
36-45 13 20.3
46-55 13 20.3
56-65 13 20.3
65+ 5 7.8
What is your church status?
Member 57 89.1
Visitor 6 9.4
What is your marital status?
Never married 4 6.3
Married 21 32.8
Widowed 3 4.7
Divorced/separated 12 18.8
Single in a committed relationship 12 18.8
Single (not in a committed relationship 12 14.7
What is your racial identity?
American Indian or Alaska Native 0 0.0
Asian 0 0.0
Black or African American 63 100
Hispanic or Latino 0 0.0
Native Hawaiian or Other Pacific Islander 0 0.0
Some Other Race 0 0.0
White 1 1.6
(table continues)

75
Variable
n
Percent
What region of the city do you live in?
Northside 27 42.2
Eastside 15 23.4
Southside 14 21.9
Westside 7 10.9
What level of education have you achieved to date?
Less than 9th grade 1 1.6
Some High School, no diploma 10 15.6
High School Graduate (or GED) 20 31.3
Some College, no degree 12 18.8
Associate Degree 4 6.3
Bachelor’s Degree 9 14.1
Master’s Degree 7 10.9
Doctorate 1 1.6
What is your yearly household income?
Less than $15,000 16 23.5
$15,000 - $24,999 14 20.6
$25,000 - $34,999 6 8.8
$35,000 - $49,999 16 23.5
$50,000 - $74,999 7 10.3
$75,000 - $99.999 4 5.9
$100,000- $149,999 3 4.4
$150,000- $249,999 2 2.9
More than $250,000 0 0.0
Note. n = 64.

76
The sociodemographic data for the experimental group representing the church
with an HIV/AIDS prevention program were obtained by asking eight questions in the
last part of the survey. The demographic questions were asked to determine if the two
samples were essentially identical, so if there was any significant difference in the
attitudes and perceptions, those could be attributed to being exposed to the prevention
program. Table 9 provides the mean and standard deviation of each of the demographic
variables as well as shows if there is a significant difference between the two groups.
Table 9
Descriptive and Demographic Characteristics and Results From Difference
of Means t-Test
Groups
Experiment Control
Characteristics Mean SD Mean SD Sign.
Gender 1.2794 .45205 1.3750 .48795 .024*
Age range 3.5147 1.47104 3.3438 1.58584 .422 n.s
Church status 1.1618 .37097 1.0976 .49015 .207 n.s
Marital status 3.3088 1.67739 3.6719 1.67194 .941 n.s
Race identify 3.0000 .00000 3.0625 .50000 .038*
Region of city 3.5588 11.78968 2.0938 1.21784 .174 n.s
Education attainment 3.8235 1.32644 4.0625 1.72631 .006*
Yearly house hold income 3.2647 1.93643 3.2656 1.92924 .968 n.s
Note. p <. 05; n.s. = not significant.

77
Analysis indicated that the experimental group was slightly more educated than
the control group. The results further revealed there are more men in the control than the
experimental group, and therefore this could impact the results based on the literature
(i.e., men are less likely to practice safe sex). The race of the participants in the study was
predominantly African Americans in both groups with one white person in the control
group and the significant finding in the table above is related to how the data was coded
rather than any meaningful differences in the data. Overall, the two groups are
statistically identical except the experimental group is better educated and is comprised of
more women. Since both factors may be associated with a person likely to practice safe
sex it may have some impact on the results.
Discrepancies in Data Collection
The experiment and control site church attendee samples were comprised of all
English speaking persons and they were able to read and write. The total number of
respondents from the combined church groups was 132; however the anticipated sample
from the experiment site was 66 and 66 from the control site. The distribution of
responses was slightly different than anticipated. The actual sample was 68 participants
from the experiment site and 64 from the control site.
Results
Before the hypothesis could be tested, the underlying statistical assumptions of
the study were addressed. The first was to produce a Cronbach’s alpha for each of the
scales used to test the key dependent variables in the study: attitude, subjective norm, and

78
perceived behavior control and intention. Once the questions used to create these scales
are established as valid, then the statistical assumptions for the t-test were considered.
Cronbach’s alpha measures internal consistency. It is commonly used as an
estimate of the reliability of a test for the closeness of a set of items in a group. The
attitude, subjective norm, perceived behavior control and intention scales/constructs were
considered in turn.
Attitude
A numerical value was assigned to each potential choice in the attitude, subjective
norm, perceived behavior control and intention scales. The Likert scales had seven
potential choices such as (strongly agree, agree, neutral, disagree, and strongly disagree).
The final average score represented the attitude, subjective norm, perceived behavior
control and intention overall level of agreement toward the subject matter. A mean figure
for all the responses was computed at the end of the survey.
The attitude scales are the result of participants answering the questions listed in
the survey. The scale consisted of four questions. The first question asked the degree to
which the respondent felt that having sex with only one partner (a monogamous
relationship) was “ineffective to very effective in preventing HIV.” Question number two
asked: “Buying a condom or dental dam (a latex covering used to prevent exchange of
bodily fluids) is effective or ineffective. “Question number three asked, “Using or asking
a partner to use a condom or dental dam is ineffective or effective.” Question number
four asked if “A partner’s sexual history will influence my decision to engage in sexual
activity with them.” Cronbach’s alpha was .87 for the scale as shown in Table 10. Since

79
the Cronbach’s alpha is higher than 0.7 these survey questions are measuring attitude
reliably.
Subjective Norm
The subjective norm scales are the result of participants answering the questions
listed in the survey. The subject norm scale consisted of three questions about what was
important about using a condom or dental dam with casual or regular partners in the
forthcoming month. The first question in the scale asked, “Most people who are
important to me think that that I should or should not use a condom or dental dam during
sexual relations with casual or regular partners each time in the forthcoming month.”
The second asked, “It is expected of me that I use a condom or dental dam during sexual
relations with casual or regular partners each day in the forthcoming month. The third
question was, “The people in my life whose opinions I value would, disapprove or
approve of my using a condom or dental dam during sexual relations with casual or
regular partners each time in the forthcoming month.” Cronbach’s alpha for the scale was
.79 as shown in Table 10. Since the Cronbach’s alpha is higher than 0.7 these survey
questions are measuring subjective norm reliably.
Perceived Behavior Control
The perceived behavior scales are the result of participants answering the
questions listed in the survey. The perceived behavior control was measured using a scale
that consisted of four questions for participants to answer related to their feelings about
using condoms or dental dams during sexual relations. The first question for the scale
asked: “For me to use a condom or dental dam during sexual relations with casual or

80
regular partners each time in the forthcoming month would be impossible or possible.”
The second asked, “If I wanted to I could use a condom or dental dam during sexual
relations with casual or regular partners each time in the forthcoming month, definitely
false or definitely true.” The third question asked, “How much control do you believe you
have over using a condom or dental dam during casual or regular sexual relations each
time in the forthcoming month, no control or complete control? The fourth question was,
“It is mostly up to me whether or not I use a condom or dental dam during sexual
relations each time in the forthcoming month, strongly disagree versus strongly agree.”
Cronbach’s alpha for the scale was .86 as shown in Table 10. Since the Cronbach’s alpha
is higher than 0.7 these survey questions would appear to be measuring perceived
behavior control reliably.
Intention
The intention scales are the result of participants answering the questions listed in
the survey. The intention scale was comprised of two Likert items. The first measured to
what extent, “I intend to use a condom or dental dam each day in the forthcoming
month.” The second asked, “For me to use a condom or dental dam during sexual
relations with my casual or regular partners each time in the forthcoming month dam was
beneficial, pleasant, good, valuable and enjoyable while many others believed condoms
or dental dams were harmful, unpleasant, bad, worthless or unenjoyable.” Due to
problems with the survey results, the data available for these two questions could not
generate a Cronbach’s alpha. Since this scale could not be tested, it is not possible to
determine if the survey appropriately measured intention. As a result, this variable

81
cannot be used in the analysis and the associated hypothesis could not be tested. (see
Table 10).
Table 10
Cronbach’s Alpha for Attitude, Subjective Norm, Perceived Behavior Control and
Intention
Variable scale Cronbach’s Alpha
Attitude .87
Subjective norm .79
Perceived behavior control .86
The three underlying assumptions for the independent t test are as follows: The
test variable is normally distributed in each of the two church populations as defined by
the experiment and control sites; the variances of the test variables are normally
distributed, and the test variable scores are independent of each other (see Table 11). The
Shapiro-Wilk test of normality was used to assess the test variables to determine normal
distribution.

82
Table 11
Test of Normality for Attitude, Subjective Norm, Perceived Behavior Control
Groups
Experiment Control
Shapiro-Wilk Shapiro-Wilk
Subscales Statistic df p Statistic df p
ATT .727 68 .000 .572 64 .000
SN .779 68 .000 .802 64 .000
PBC .768 68 .000 .775 64 .000
Note. df = degrees of freedom; p,<.05; ATT = Attitude; SN = Subjective Norm; PBC = Perceived Behavior
Control
If the data is normally distributed, the p value is above 0.05. Thus, the Shapiro-
Wilk test for normality showed that the two church groups were positively skewed and it
did not indicate normality. The findings shown in the Shapiro-Wilk test indicate that the
distributions are not normal and it was determined that the independent t tests are not an
appropriate test. Since the dependent variables are not normally distributed, the Wilcoxon
signed ranked test was used to test the hypotheses. The Wilcoxon signed ranked text can
be used to compare different participants within a match-pair study design and does not
assume normality in the data. (see Table 12).

83
Table 12
Wilcoxon Signed Ranks Test for Attitude, Subjective Norm, and Perceived Behavior
Control for the Experiment and Control Groups
Groups
Experiment Control
Subscales MR MR Z p
ATT 23.22 (positive ranks) 20.31 (negative ranks) -1.298 .194
SN 30.85 35.66 -1.710 .087
PBC 29.08 33.17 -3.320 .001
Note. MR =Mean Rank; Z = Z score; p < 0.10; ATT = Attitude; SN = Subjective Norm; PBC = Perceived
Behavior Control;
A Wilcoxon matched pairs signed rank test was conducted by using SPSS version 21
(Green & Salkind, 2008) to determine whether there was a difference in the ranking of
two church groups by the researcher. The results indicate that the P score for Attitude is
greater than 0.10, which means there is no significant difference between the mean values
and I cannot reject the null hypothesis. The P score for Subjective norm was less than
0.10, which means there is a significant difference between the mean values and I can
reject the null hypothesis. The P score for Perceived Behavior Control was less than 0.10,
which means there is a significant difference between the mean values and I can reject
the null hypothesis.
Hypothesis
Hypothesis 1
H01: There is no statistically significant difference between attitude scores towards
condom use or dental dam use for individuals who have participated in a church-based

84
HIV/AIDS prevention program and those who have not. The null hypothesis cannot be
rejected in favor of the alternative hypothesis. As shown in Table 12 there is no statistical
difference between the control group and the experimental group in regards to attitude.
HA1: There is a statistically significant difference between attitude scores towards
condom use or dental dam for individuals who have participated in a church-based
HIV/AIDS prevention program and those who have not.
Hypothesis 2
H02: There is no statistically significant difference between subjective norm scores
towards condom use or dental dam for individuals who have participated in a church-
based HIV/AIDS prevention program and those who have not. The null hypothesis was
rejected in favor of the alternative hypothesis because the P value was less than 0.10.
HA2: There is a statistically significant difference between subjective norm scores
towards condom use or dental dam for individuals who have participated in a church-
based HIV/AIDS prevention program and those who have not.
Hypothesis 3
H03: There is no statistically significant difference between perceived behavioral
scores towards condom use or dental dam for individuals who have participated in a
church-based HIV/AIDS prevention program and those who have not. The null
hypothesis was rejected in favor of the alternative hypothesis because the P value was
less than 0.10.

85
HA3: There is a statistically significant difference between perceived behavioral
scores towards condom use or dental dam for individuals who have participated in a
church-based HIV/AIDS prevention program and those who have not.
Hypothesis 4
H04: There is a statistically significant difference between intention scores towards
condom use or dental dam for individuals who have participated in a church-based
HIV/AIDS prevention program and those who have not. The null and alternate
hypotheses were dropped from the analysis because intention was not a valid construct
for the survey.
HA4: There is a statistically significant difference between intention scores
towards condom use or dental dam for individuals who have participated in a church-
based HIV/AIDS prevention program and those who have not. This hypothesis could not
be tested due to technical problems with the data that would not apply for statistical
testing in SPSS (Green & Salkind, 2008). The problem may have been related to the way
the data was coded/organized and distributed.
There is a chance that the exposure to church-based HIV/AIDS prevention did not
statistically influence attitude, in the experiment or control group. The experiment group
was found to be more highly educated than the control group, which could have impacted
higher positive responses to some of the survey questions.
Summary
In this study, two principle questions were addressed. The first question
investigated to what extent did exposure to church-based HIV/AIDS prevention programs

86
influence attitude, subjective norm, and perceived behavioral control of adult Christian
church attendees in the South? The second question asked, to what extent did exposure
to church-based HIV/AIDS prevention programs influence intention to engage in safe sex
practices (condom or dental dam use) of adult Christian church attendees in the South?
This question was not addressed in the study because two of the four proposed questions
were dropped per the pilot test draft. With only two variables there should have been
enough to do the analysis; however there were issues with how the data was
coded/organized/distributed and the needed test to test for internal consistency could not
be done. The findings in the study from the first question inferred that there is a chance
that the exposure to church-based HIV/AIDS prevention did not statistically influence
attitude, in the experiment or control group. The experiment group was found to be more
highly educated than the control group, which could have impacted higher positive
responses to some of the survey questions.

87
Chapter 5: Discussion, Conclusions, and Recommendations
Introduction
The purpose of this study was to research the influence of exposure to church-
based HIV/AIDS prevention of adult church attendees in a metropolitan city in the South
using the TPB as the framework by establishing and comparing the differences in
attitude, subjective norm, and perceived behavior control scores for two churches. The
theoretical framework explained that intention is the primary determinant of behavior and
is influenced by attitude, subjective norm, and perceived behavioral control. The survey
was distributed to two (experiment group and control group) church congregations in
June 2014.
Interpretation of Findings
The results and findings of the study were presented in Chapter 4. A Wilcoxon
Ranks Test was conducted to analyze the data and to test the three hypotheses. The
research question addressed by the study was as follows: To what extent does exposure to
a church-based HIV/AIDS prevention program influence attitude, subjective norm, and
perceived behavioral control of adult Christian church attendees in the South? A second
research question and fourth hypotheses could not be tested due to problems with the
data.
Attitude
Attitude, according to Ajzen (2011), is an expression of a positive or negative
value for a particular behavior. The Wilcoxon ranks test relating to the attitudes segment
of the survey for the present study determined that there was not a statistically

88
significant difference between the experiment and control group mean scores on the
survey. This study showed that a positive attitude value for a particular behavior can be
improved by providing educational prevention training relative to church-based
HIV/AIDS prevention for adults.
African American churches have been influential in working with diverse
memberships of parishioners of all ages and socioeconomic stratums (Berkley-Patton et
al., 2008). A needs assessment was administered to church leaders who attended a
Baptist Convention to learn more about TIPS and how to present HIV prevention
education to their congregations. Four hundred church community members and 3,000
church members were exposed to the TIPS program. My research study is consistent
with Berkley-Patton et al., 2008 to learn about the TIPS program from a Christian
church group with a church-based HIV/AIDS prevention program. No significant
differences were found between both Christian church congregations relative to attitudes
about HIV/AIDS prevention.
Subjective Norm
The subjective norm is defined as a social pressure variable and is dependent
upon the total normative beliefs (Ajzen, 2011). The subjective norm variable was
addressed in the study by asking three questions measuring the importance of family and
friends’ opinions about using condoms or dental dams as safe sexual practices. The
literature review demonstrated the dynamics of coping self-efficiency and social support,
which was consistent with Miner et al. (2009) who examined the association between

89
social norms and unsafe sexual practices. The study concluded that the TPB increases
understanding about safe sex and their belief that they can control the specific behavior.
Perceived Behavior Control
Perceived behavior control was measured with the use of four questions regarding
the individual’s confidence about whether he or she was capable of performing a
particular behavior. This aspect of the study’s result was consistent with Kennedy and
Jenkins (2011) who wrote about promoting African American women and sexual
assertiveness in reducing HIV/AIDS. My research study showed there was a
statistically significant difference between perceived behavioral scores towards condom
use or dental dam for individuals who have participated in a church-based HIV/AIDS
prevention program and those who have not. The experimental group had more female
participants and was more highly educated than the control group.
Intention
My research study was inconsistent with Kiene et al. (2008) who attempted to
explain the variability in condom use attitudes, self-efficacy, and behavioral intentions
that can vary day-to-day (perceived behavioral control) and behavioral intentions on a
day-to-day basis. This study concluded that individuals who tended to have stronger
behavioral intentions than those who tended to have weaker behavioral intentions may
increase the likelihood of condom use. My study attempted to analyze intention
behaviors; however, the variable intention was not analyzed due to problems related to
the way that it was coded and distributed as well as not being able to be analyzed in the

90
research question and the hypothesis. The results of this study connect to the literature
(Kiene et al., 2008).
Limitations of the study
There were several limiting factors identified with this study. First, the study was
limited to adult members of two Christian churches in a metropolitan area of the
American South. A second limitation was that the data were not collected on the
participants’ attitudes, subjective norms, perceived behavioral control, intentions, and
sexual behaviors of adolescents. A third limitation was self-reporting because there may
have been some participants who underreported actual experiences. A fourth limitation
with this study was it did not include adults in other HIV/AIDS prevention programs.
Additionally, the fifth limitation of the study was the problem identified with the
intention research question and associated hypothesis. The intention scale was comprised
of two Likert items. More specifically, a problem was identified with the way the
intention scale was coded/organized/distributed; therefore, the data could not be analyzed
along with the research question related to intention and the hypothesis.
The final limitation with the study was the experimental group being more likely
to engage in safe sex than the control group due to demographic factors. Overall, the two
groups were statistically identical, except the experimental group was better educated and
was comprised of more women. Since both factors may be associated with a person likely
to practice safe sex, it may have some impact on the results. The results of the study are
generalizable to the two groups who participated in the study instead of the larger church
attendee population.

91
Recommendations
I suggest several recommendations for further research that include expanding the
number of Christian churches involved in the study, either within the same religious
denomination or a cross section of other church denominations within several states
related to successfully reducing HIV/AIDS by presenting a prevention message about
certain sexual behaviors that predisposes people to certain diseases that are serious and
sometimes catastrophic.
I also recommend collecting data over a longer timeframe to develop a larger
sample size, especially for the adult population. Thus, a larger dataset may enable
generalization of the study findings. I recommend further research be expanded to
include mixed methods to further explore the concepts and components that influence
exposure to church-based HIV/AIDS prevention for adults such as attitudes, subjective
norms, perceived behavior control, and intentions to engage in safe sex practices.
The information provided by this study may assist public health officials as well
as other researchers in conducting further research to assist with designing preventative
campaigns that address the observed behaviors and develop interventions that are tailored
to targeted group’s behavioral goals. Another recommendation is that behavior
modification should be promoted via segment-targeted campaigns to demonstrate the use
of tools and other protective barriers that increase HIV/AIDS awareness in all
populations about how to prevent the infection and disease. The findings from this study
may help to add to the knowledge base given the limitations in previous studies related to

92
attitudes, subjective norms, and perceived behavioral control relative to engaging in safe
sex practices among African American adults living in the South.
Implications for Social Change
HIV/AIDS is still on the rise in the Southern United States as evidenced by recent
official statistics pointing to an increase in number of new cases of HIV (Alabama Public
Health Department, 2012). However, research on the factors operating on the local
population is limited, and only a few studies have been done on adults attending Christian
churches in the South. The results of this study underscore the possibility that there is still
much to be learned about differentiating factors such as gender, age range, church status,
marital status, race identity, region living in the city, education attainment, and household
income status influencing the targeted age group of 18 years old or older.
Awareness of the trends in sexual behavior among adults who attend mainline
Christian church services can serve to identify future public health policies that would
promote effective intervention strategies based on specific cultural and behavioral
patterns observed among this population and others. The study focused on attitudes,
subjective norms, and perceived behavioral controls relative to engaging in safe sex
practices as the result of exposure to church-based HIV/AIDS prevention programs.
Conclusions
In this quantitative cross-sectional study including an experimental and control-
group with a convenience adult sample, I explored the relationship between the exposure
and influence of church-based HIV/AIDS prevention relative to attitudes, subjective
norms, and perceived behaviors as it related to engaging in safe sex practices. The results

93
indicated that the two adult populations were representative of the population of interest.
Wilcoxon Ranks Test was conducted to analyze the data and to test the three hypotheses.
While there was not a statistical difference between the experiment group and control
group related to attitudes, there was a statistical difference between the mean scores of
subjective norm and perceived behavior control. That information can inform continuing
research and education in HIV/AIDS awareness and in turn help with the prevention of
HIV/AIDS.
The framework of the TPB partially explained the behavior of adults in this study.
The findings will help fill an existing gap in the literature for the two particular
populations because there are no previous studies on attitude, subjective norm, and
perceived behavioral control, relative to exposure to church-based HIV/AIDS prevention
among predominantly African American adult church congregations in the South.

