


Challenges in Creating Herd Immunity to SARS-CoV-2
Introduction
Opening: In order to ease off the pandemic, many countries
implemented health policies ensure the societies can recover
successfully, vaccination became the most efficient and effective tool.
Compulsory and voluntary vaccination programs are the current
leading tactics. Although voluntary options may not attribute high
vaccine uptake rate as compulsory program, compelling strategies
may potentially backfire the results such as public anger, distrust and
hesitancy (Jennings et al., 2021; Sherman et al., 2020; Motta et al.,
2021).Safety concerns also play an important role in public attitude
(Neumann-Bohme et al., 2020; Robertson et al., 2021; Kerr et al.,
2021; Craig, 2021). Many incentive programs had been promoted but
results are not prominent, such as money (Sprengholz et al., 2021),
frame (Palm et al., 2021; Davis et al., 2021), social norm (Sinclair
&Agerstrom et al., 2021), certificate (Mills &Ruttenauer et al., 2022).
This research is going to examine under what circumstancesthe type
of vaccination (Savulescu, 2021; Savulescu et al., 2021) will make
people hesitate to take the vaccine. Mainly focus on public anger
(Graeber et al., 2021; Renstrom& Back, 2021; Abadi et al., 2021; Han
et al., 2020; Smith et al., 2020) andidentification to the government.
In order to mitigate the pandemic, numerous governments pursued
public health policies for society to recover successfully. Therefore,
humanity has observed various development programs launched
worldwide to create proven practical, cost-effective vaccines and
obtain regulatory approval quickly. It is reasonable to state that the
scientific communities have discovered an approach to an impossible

mission. Several vaccines have completed trial phases in record time
for the first anniversary of the WHO announcement of the COVID-19
pandemic (Anderson et al., 2020). However, this rapid progress has
been weighed down by the grave crisis: infodemia in the age of social
media. Pseudoscientific misinformation and conspiracy theories have
blurred public perceptions of the disease, distorted general
understanding of preventive measures, and undermined public
attitudes toward vaccination programs.
The success of an immunization campaign relies not solely on the
availability and accessibility of vaccines but correspondingly on
people’s attitudes. The World Health Organization (WHO) defines
vaccine hesitancy as behavior influenced by a set of factors (Cislak et
al., 2021). They include mistrust (people do not trust the vaccine,
manufacturer, or supplier), complacency (do not see the need for the
vaccine), and availability of drugs. The world crisis caused by the
coronavirus affects people’s attitudes toward the health care system,
science, and medicine in numerous ways. The novelty of the disease
and concerns about the safety and efficacy of antivirals have led to
many people in the United States stating their reluctance to be
vaccinated against COVID-19. This phenomenon is common in other
countries: in May 2021, about 25% surveyed stated they would refuse
to be vaccinated – they doubted the reliability of the emergency
vaccine (Cislak et al., 2021). Italian scientists have also analyzed the
concern of hesitancy to immunize during the COVID-19 pandemic.
They searched the PubMed electronic database for original peer-
reviewed articles by keyword – their review ended up with 15 studies

from the United States, United Kingdom, Turkey, France, Malta, Italy,
Canada, Japan, Spain, and Switzerland. The review showed a high
overall level of indecision about COVID-19 vaccines. These results
are predictable: the number of antivaccers worldwide ranges from 7%
to 33% (D’Ancona et al., 2019). According to the analysis, there is a
high degree of skepticism about the flu vaccine among African
Americans. Unemployed and low-income people rarely agreed to be
vaccinated; however, some studies noted that income did not affect
attitudes toward vaccination. Moreover, participants with lower levels
of education were also less likely to agree to be vaccinated (D’Ancona
et al., 2019). There are numerous diverse studies of various
populations and reasons for their different attitudes toward
immunization. However, no single relevant source analyzes the
relationship between anger and individuation on vaccination
decisions. Therefore, the correlation of these variables became the
central and relevant topic for the thesis.
One of the most prominent aspects of the study is the influence of
political beliefs: support for populist parties can be an indirect
indicator of hesitancy to vaccinate, at least in Western European
countries. Therefore, increasing populist support among the
population can be regarded as a threat to public health. Forcing people
to be vaccinated has often been a cause of public anger, which has
also become a significant issue in today’s world. Therefore, there is a
need for a program that will meet the population’s needs and address
the high level of anger, which is often caused by the need to obey
(Dror et al., 2020). Public anger is an essential variable to identify and
influence people’s beliefs. It should be analyzed as an integral part of

vaccination programs, which can be changed qualitatively according
to the indicators.
Furthermore, coercion is foremost a psychological influence on
another person to obey the desired action without informed and
deliberate consent. It can include manipulation, threats, blackmail,
pressure, and ultimatums (Feng et al., 2018). Altering a person’s
feelings and thinking, not just their actions, cannot be attained by
violence, which is why coercion causes anger. There must be the
person’s desire, interest, involvement, and will in this process. Lately,
the fight against the coronavirus epidemic has become identified with
the introduction of a more comprehensive regime of QR codes
confirming that their owners are inoculated against the SARS-CoV-2
virus (Feng et al., 2018). Having QR codes, a person has rights to
move freely around the country and their place of residence. People
without QR codes are affected in their freedoms significantly. There
are natural ethical questions connected with the admissibility of
forcing people to go through the experimental medical procedure.
There are also political concerns that widespread opposition to
compulsory vaccination, primarily if it affects children, could result in
destabilization, taken advantage of by forces hostile to the government
and its constitutional order.
Promoting vaccination is a crucial strategy for gaining collective
immunity against COVID-19 and a condition for overcoming the
pandemic. Advocacy ranges from the mere provision of information to
policy prescriptions (Giubilini, 2020). Nevertheless, some degree of
autonomous choice is preferable since public health is guided by the

principle of the least restrictive alternative. It states that to achieve the
general good of collective immunity, people must choose the
measures that limit individual rights and freedoms the least (Glenn &
Kenney, 2018). The ability to make one’s own decisions and conduct
daily life following one’s values and preferences is central to human
dignity. Any restrictions on choice lead to agitation, which in turn can
affect the vaccination process.
Several COVID-19 vaccines are developed with modern technologies
and involve new processes in manufacturing; therefore, some
uncertainty surrounds them. Vaccine efficacy is clarified through
randomized controlled trials at the approval stage, and then it is
refined through field studies (Goralnick et al., 2017). However,
mutations in the virus may reduce or influence the effectiveness of the
immunization. People have different emotions because this is a very
controversial issue and no one can accurately determine the
consequences of vaccination for everyone. Therefore, coercion stirs
the mind and causes immediate reactions in individuals. Respecting
people’s autonomy in deciding is crucial with all the uncertainties
surrounding vaccines. Research indicated that some nudges can
interfere with autonomous decision-making, cause negative emotions,
and force people to make choices they may not want to make
(Gualano et al., 2019). While they may quickly lead to desirable
results in terms of collective behavior, such interventions may reduce
the level of cooperation later. Even though such interventions may
promote vaccination now, they may reduce the effectiveness of
controlling the spread of other infections and the level of
immunization against them in the future.

To maintain social well-being, governments should use nudge-
comparison instead of nudge-loss of influence, which emphasizes the
negative impact on society of a personal refusal to vaccinate.
Moreover, there is a direct link between identification with the
government and the stringency of measures. It can be assumed that the
higher the credibility is, the easier it is to convince people to get
vaccinated. Conversely, where it is low, one must resort to harsher
measures. This was the case, for example, in the Congo during the
Ebola epidemic in 2018-2019 (Hasan et al., 2021). At the same time,
studies confirm that excessive pressure has the opposite effect and
undermines the desire to be vaccinated. In the UK, a survey of health
and social service workers showed that employer pressure on
employees made the latter more likely to refuse vaccination (Hasan et
al., 2021). This effect could undermine trust in medicine for years to
come – forced vaccination in Africa more than half a century ago still
negatively affects health systems. In addition, harsh coercion can
undermine trust in the government, and a vicious circle of mistrust and
intimidation will emerge. In such a case, bans can only be used as a
last resort, but the government should explain why it has decided to
use them.
Unity of communication is the key to success: a common stance by
doctors, scientists, civil servants, religious leaders, and opinion leaders
will influence the general population. Effective persuasion also
depends on the speaker’s reputation and credibility (Hosangadi et al.,
2020). In the moments of crisis, credibility is made up of
transparency, commitment, level of professionalism, and empathy.

Withholding information, inconsistent messages from management,
and disregard for people’s opinions all reduce people’s willingness to
vaccinate. Moreover, group affiliation and general thinking can also
have a significant influence on people’s actions and reasoning.
Working in a group, people can make the most unpredictable
decisions, and not all of them are rational. A so-called “risk-taking
phenomenon” emerges-the tendency to make riskier decisions if
responsibility for their consequences is shared with others.
Willingness to make risky decisions depends mainly on the individual
characteristics of meeting participants and the relationships developed
in the group (Krasser, 2021). People present at a meeting may make a
difficult decision because no one is personally responsible for it. The
process of group decision-making is similar to the operation of
individual decision-making. In both cases, the same stages are present
– understanding the problem, gathering information, proposing and
evaluating alternatives, and choosing one of the alternatives.
However, group decision-making is more complex in socio-
psychological terms, as each stage is accompanied by an interaction
between group members and, accordingly, the clash of different
views.
Despite this, it is scientifically proven that belonging to a group
directly impacts decision-making. After all, dissent often has negative
consequences and can lead to expulsion from the group. For this
reason, decisions are more often all taken by consensus, and each
particular group shares opinions and views. In the course of numerous
studies conducted by followers and social psychologists, it has been

revealed that a person often decides based on belonging to a group
(Krasser, 2021). In this group, one forms the beliefs, which one does
not later abandon. They, in turn, influence the process of decision-
making and, consequently, choice.
The essence of the phenomenon of group polarization lies in the fact
that in the process of discussion, aimed at working out a decision,
significant for the group, a kind of extremization of group opinions
occurs. They begin to gravitate to the extreme values of the preference
scale, and the number of middle, intermediate decisions significantly
decreases. For example, if a group of moderate liberal politicians
makes a joint decision, it will be more liberal (Lucia et al., 2021).
Conversely, if a group of moderately conservative politicians makes a
collective decision, the decision will be more conservative. The
primary result of polarization is the following: whatever the initial
preference of the group before the discussion, this preference is
reinforced during the discussion.
Despite a large amount of research on vaccines, there are still no
reliable sources regarding the effects of vaccination programs on the
population. Therefore, the purpose of the study is to examine the
impact of compulsory and voluntary vaccination programs on vaccine
hesitancy. The thesis will focus on the variables of public anger and
identity to establish their relationship and influence on people’s
choices. Numerous models and calculations will be used so that the
truth of the conception can be proven and provide a qualitative basis
for further research.

Hypothesis:
1. When people negatively identify themselves with the
government, compulsory vaccination program increases their
anger level.
2. When people negatively identify themselves with the
government, compulsory vaccination program increases the
hesitancy towards the vaccine uptake.
3. Compulsory (vs voluntary) vaccination leads to greater anger
and hesitation; these effects are reduced for those who identify
with the government.
Methods
Participants
Total of 124 participants were recruited via the social media website
such as Facebook, Instagram and WhatsApp. Of these, 12 responses
were excluded from the data due to incomplete responses (7), did not
consent (1), did not pass the manipulation check (4). Proceeding with
112 responses, 38 Asian or Asian British (34%), 24 Black, African,
Caribbean or Black British (21%), 25 Mixed or Multiple ethnic group
(22%), 2 Other ethnic group (2%) and 23 White (21%). Participants
aged between 18 and 56 years (M = 28.10, SD = 8.11). This study
does not interested in gender difference, thus participants were not
required to disclose their gender. Participation was completely
voluntary, while participants were incentivised by the opportunity to
win a £25 Amazon voucher in a prize draw.

Materials
An online questionnaire was applied in this study, which consists of
three scales and a vignette, representing the condition the participants
are randomly assigned to. Four major factors were measured, namely
the identification level with the government, anger level of the
government action and the hesitancy level of vaccine uptake. The
questionnaire was developed using an online questionnaire service
Qualtrics and there are total of 28 questions developed. The data from
the questionnaire were exported from Qualtrics and imported to
RStudio for data analysis.
The questions used in this study were adopted from previously
established research that generated valid and reliable results. All of the
questions were adopted from the original studies, but the wording of
the questions were modified to match the current study. This section
below provides the adjustment made to the scales.
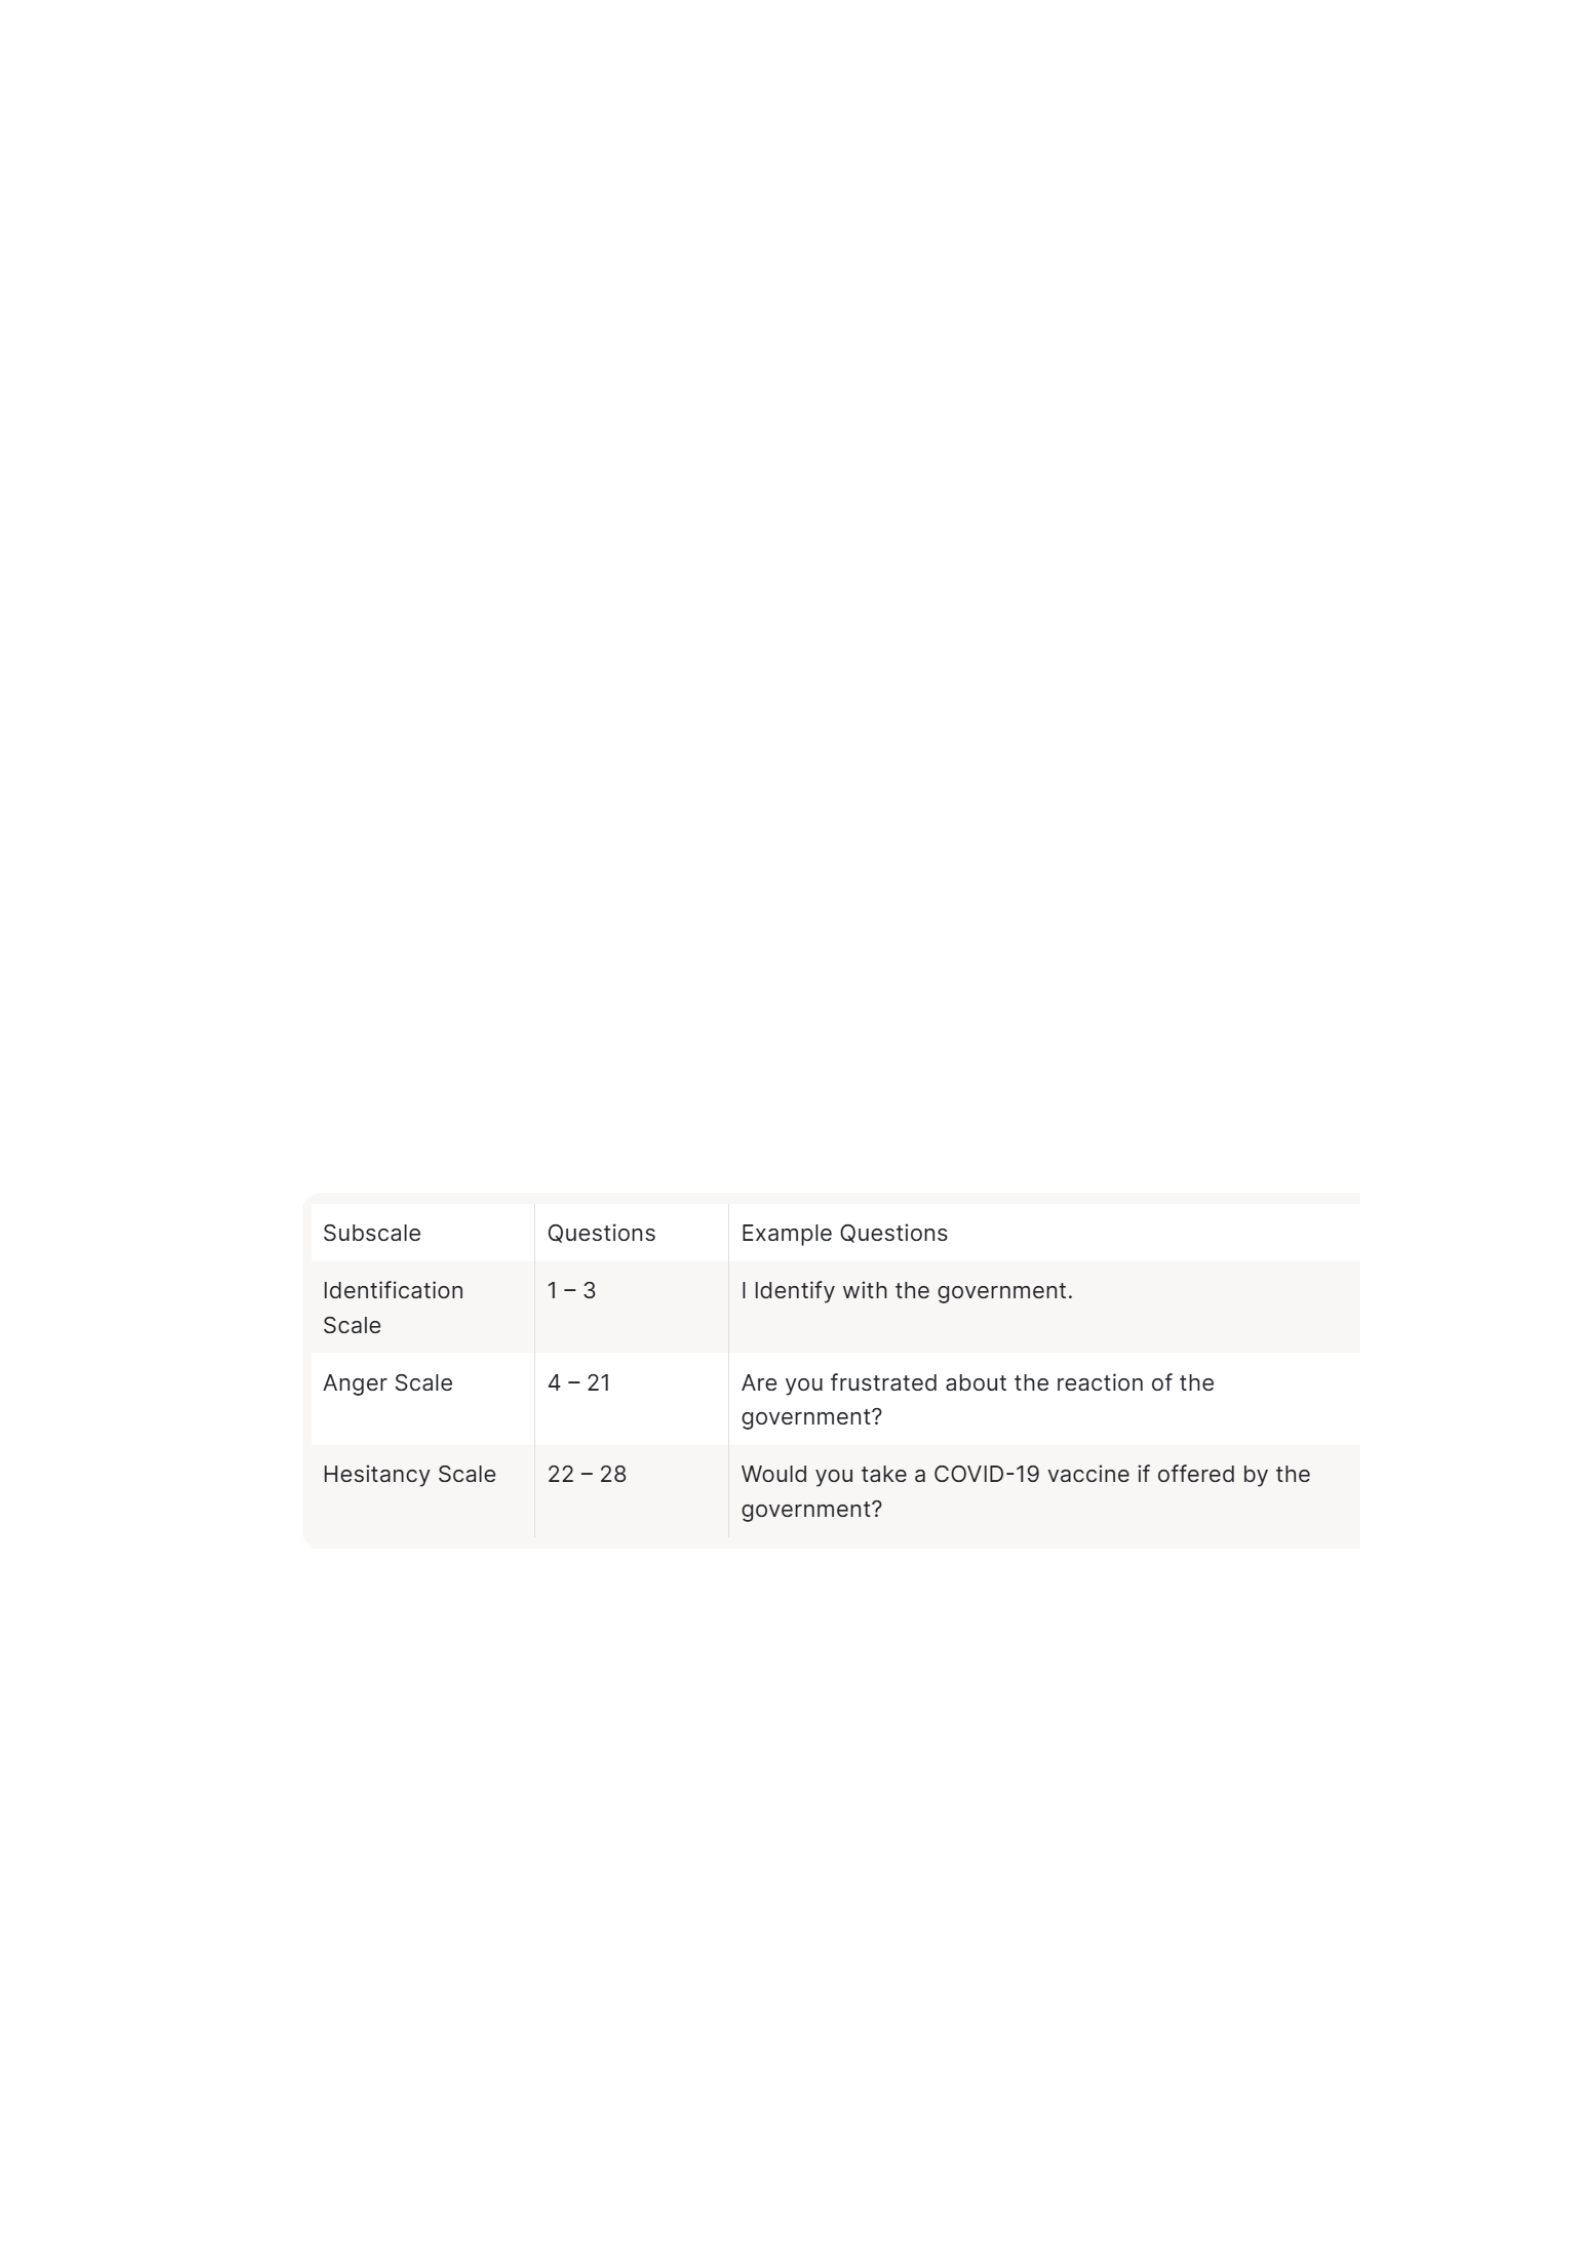
Identification Scale with the Government: The Identification Scale
consists of three questions. All the items are originated from Leach et
al. (2008). For instance “I see the government as part of my in-
group.”. The Identification scale was measured on a 7-point Likert
scale (1 = Strongly disagree and 7 = Strongly agree).
Anger Scale: An extensive 18 items Anger scale was derived from the
Salzburger State Reactance Scale (SSR Scale) (Sittenthaler et al.,
2015), which provided reliable and valid results. The SSR scale is
developed based on the nature of reactance, proposed by Dillard and
Shen (2005). For example “To what extent do you perceive the
reaction of the government as a restriction of freedom?”. The
questions were measured on a 7-point Likert scale (1 = Not at all and
7 = Very much).Three items were reversely coded before entering the
data analysis process (items 11, 15, 16, Appendix 2).
Hesitancy Scale: There are 8 items in this measurement, which were
adopted from Freeman et al. (2021). Although this is a newly
developed scale, the scale mostly focuses on the COVID-19 vaccine
hesitancy in the UK and also generated a good fit of the statistical
models. For example “If a COVID vaccine was available at my local
pharmacy, I would…”. Hesitancy was measured on a 6-item scale.
Table 1. Question examples for each subscale


The full set of questionnaire questions can be seen in Appendix 1.

Design
The present study used an independent measures questionnaire design.
The total of 112 participants were evenly distributed into either
compulsory (58) or voluntary (54) vaccination conditions.In data
analysis, participants compulsory condition was coded 1, while
voluntary condition was coded 0. All participants were required to
answer the 3 items Identification scale, 18 items Anger scale and the 7
items Hesitancy scale. To elicit the vaccination program effect, two
vignettes were designed to condition either compulsory or voluntary
vaccination program. Different wordings were used in each vignette,
while the images were kept the same for both conditions in order to
reduce confounds.
Procedure
Participants were recruited via different social media website such as
Facebook, Instagram and WhatsApp. A weblink containing the
questionnaire was sent out and the recipients were told that the
questionnaire measured their attitude towards vaccination. Participants
were required to provide consent to take part in the study once they
entered the website. Then they had to complete the three
itemsIdentification scale. After that, they were presented the
vaccination vignette which was either compulsory or voluntary
condition. Followed by the 18 items Anger scale and the 7 items
hesitancy scale at the end. Participants were also debriefed with the
purpose and the hypothesis of the study, and were reminded that their
responses and the email for prize draw were stored separately and
anonymously in the University online storage.
Result
Reliability Analysis
High reliability scores are generated from all three scales,
Identification Scale α= 0.96, Anger scale α= 0.98and Hesitancy scale
α= 0.97. Therefore, all three scales are deemed to be appropriate to
treat as three independent variables.
Descriptive Data
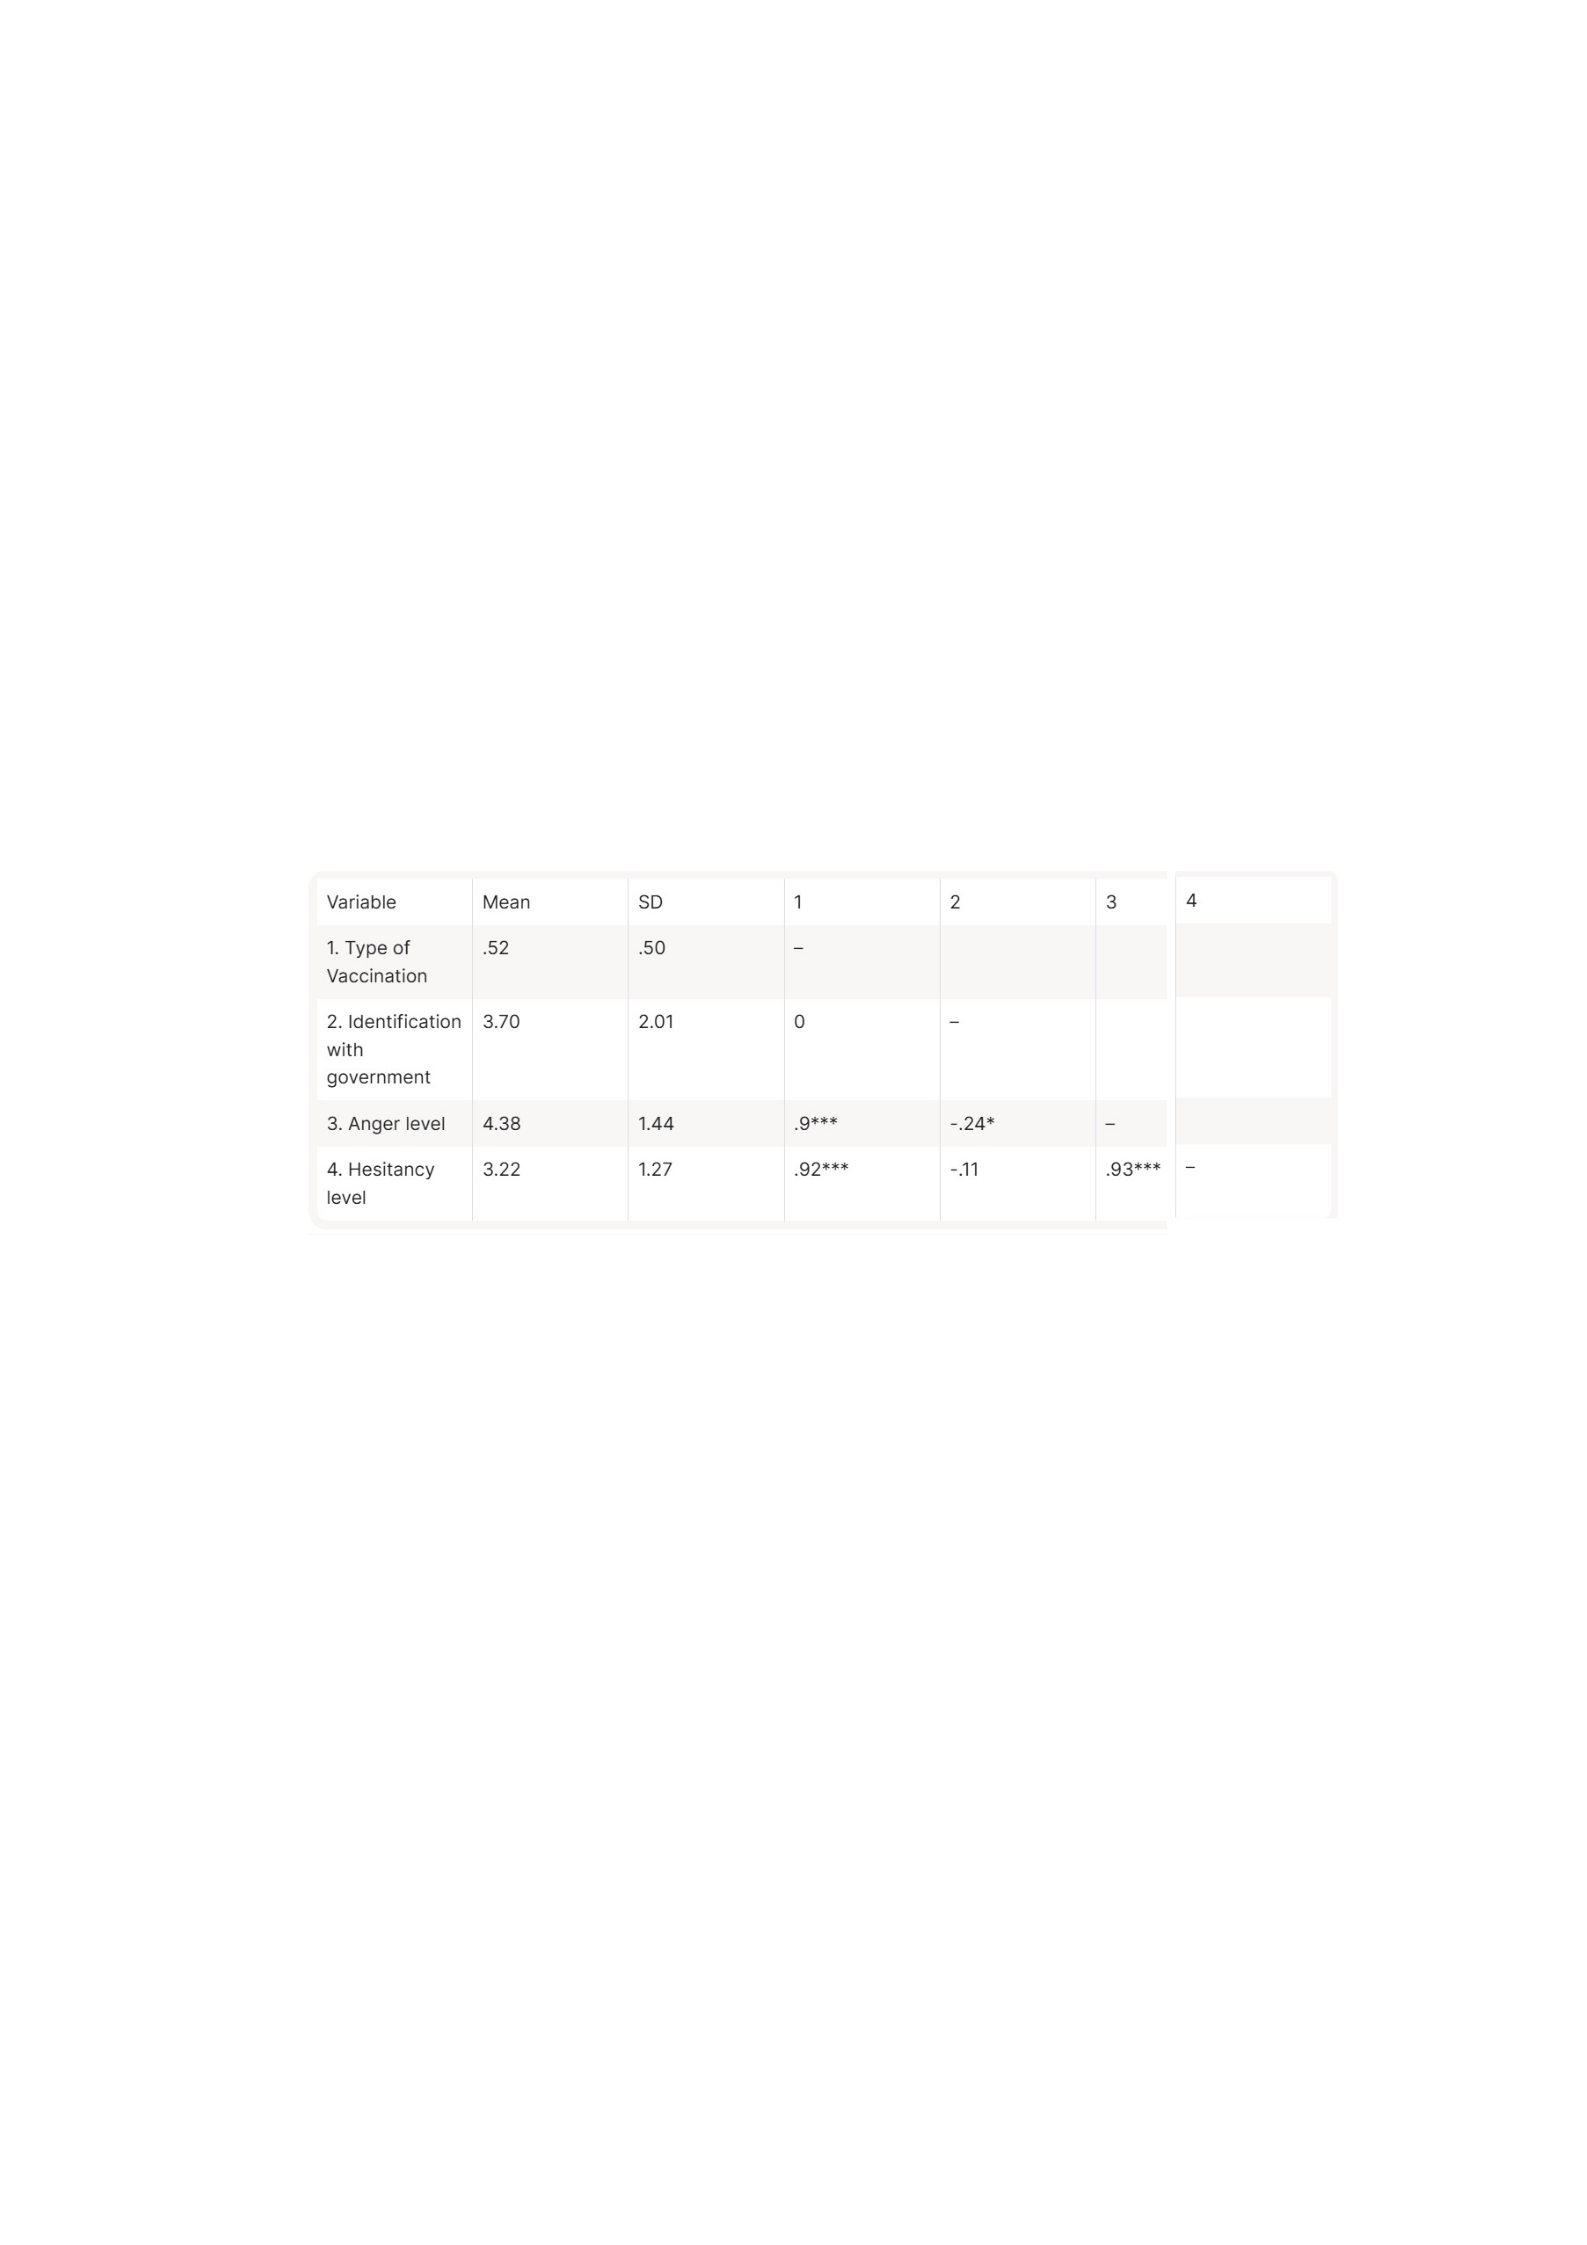
Table 2.Descriptive Statistics and Correlations between Study
Variables for Overall Sample (N = 112)
Note. *p <.05, **p <.01, ***p <.001
In general, there is a clear difference between compulsory (M = 4.34)
and voluntary (M = 2.02) vaccination on vaccine hesitancy. The
Pearson’s Correlation plot displays the overview of relationship
between each variables. It shows that only vaccination type, anger
level and hesitancy level have positive relationship; while
Identification has norelationship with vaccination type, anger level
and hesitancy level. In terms of the overall performance of
allresponses. The mean of 0.52 implies that both conditions were
evenly distributed. In the 7-points Identification scale, a mean of 3.7
shows that participants slightly identified with the government. While
participants moderately showed anger against the government, with
the mean of 4.38 in a 7 points scale. Additionally, a 6 points hesitancy
scale gathered a mean of 3.22 which is above the scale mid-point.
Moderation
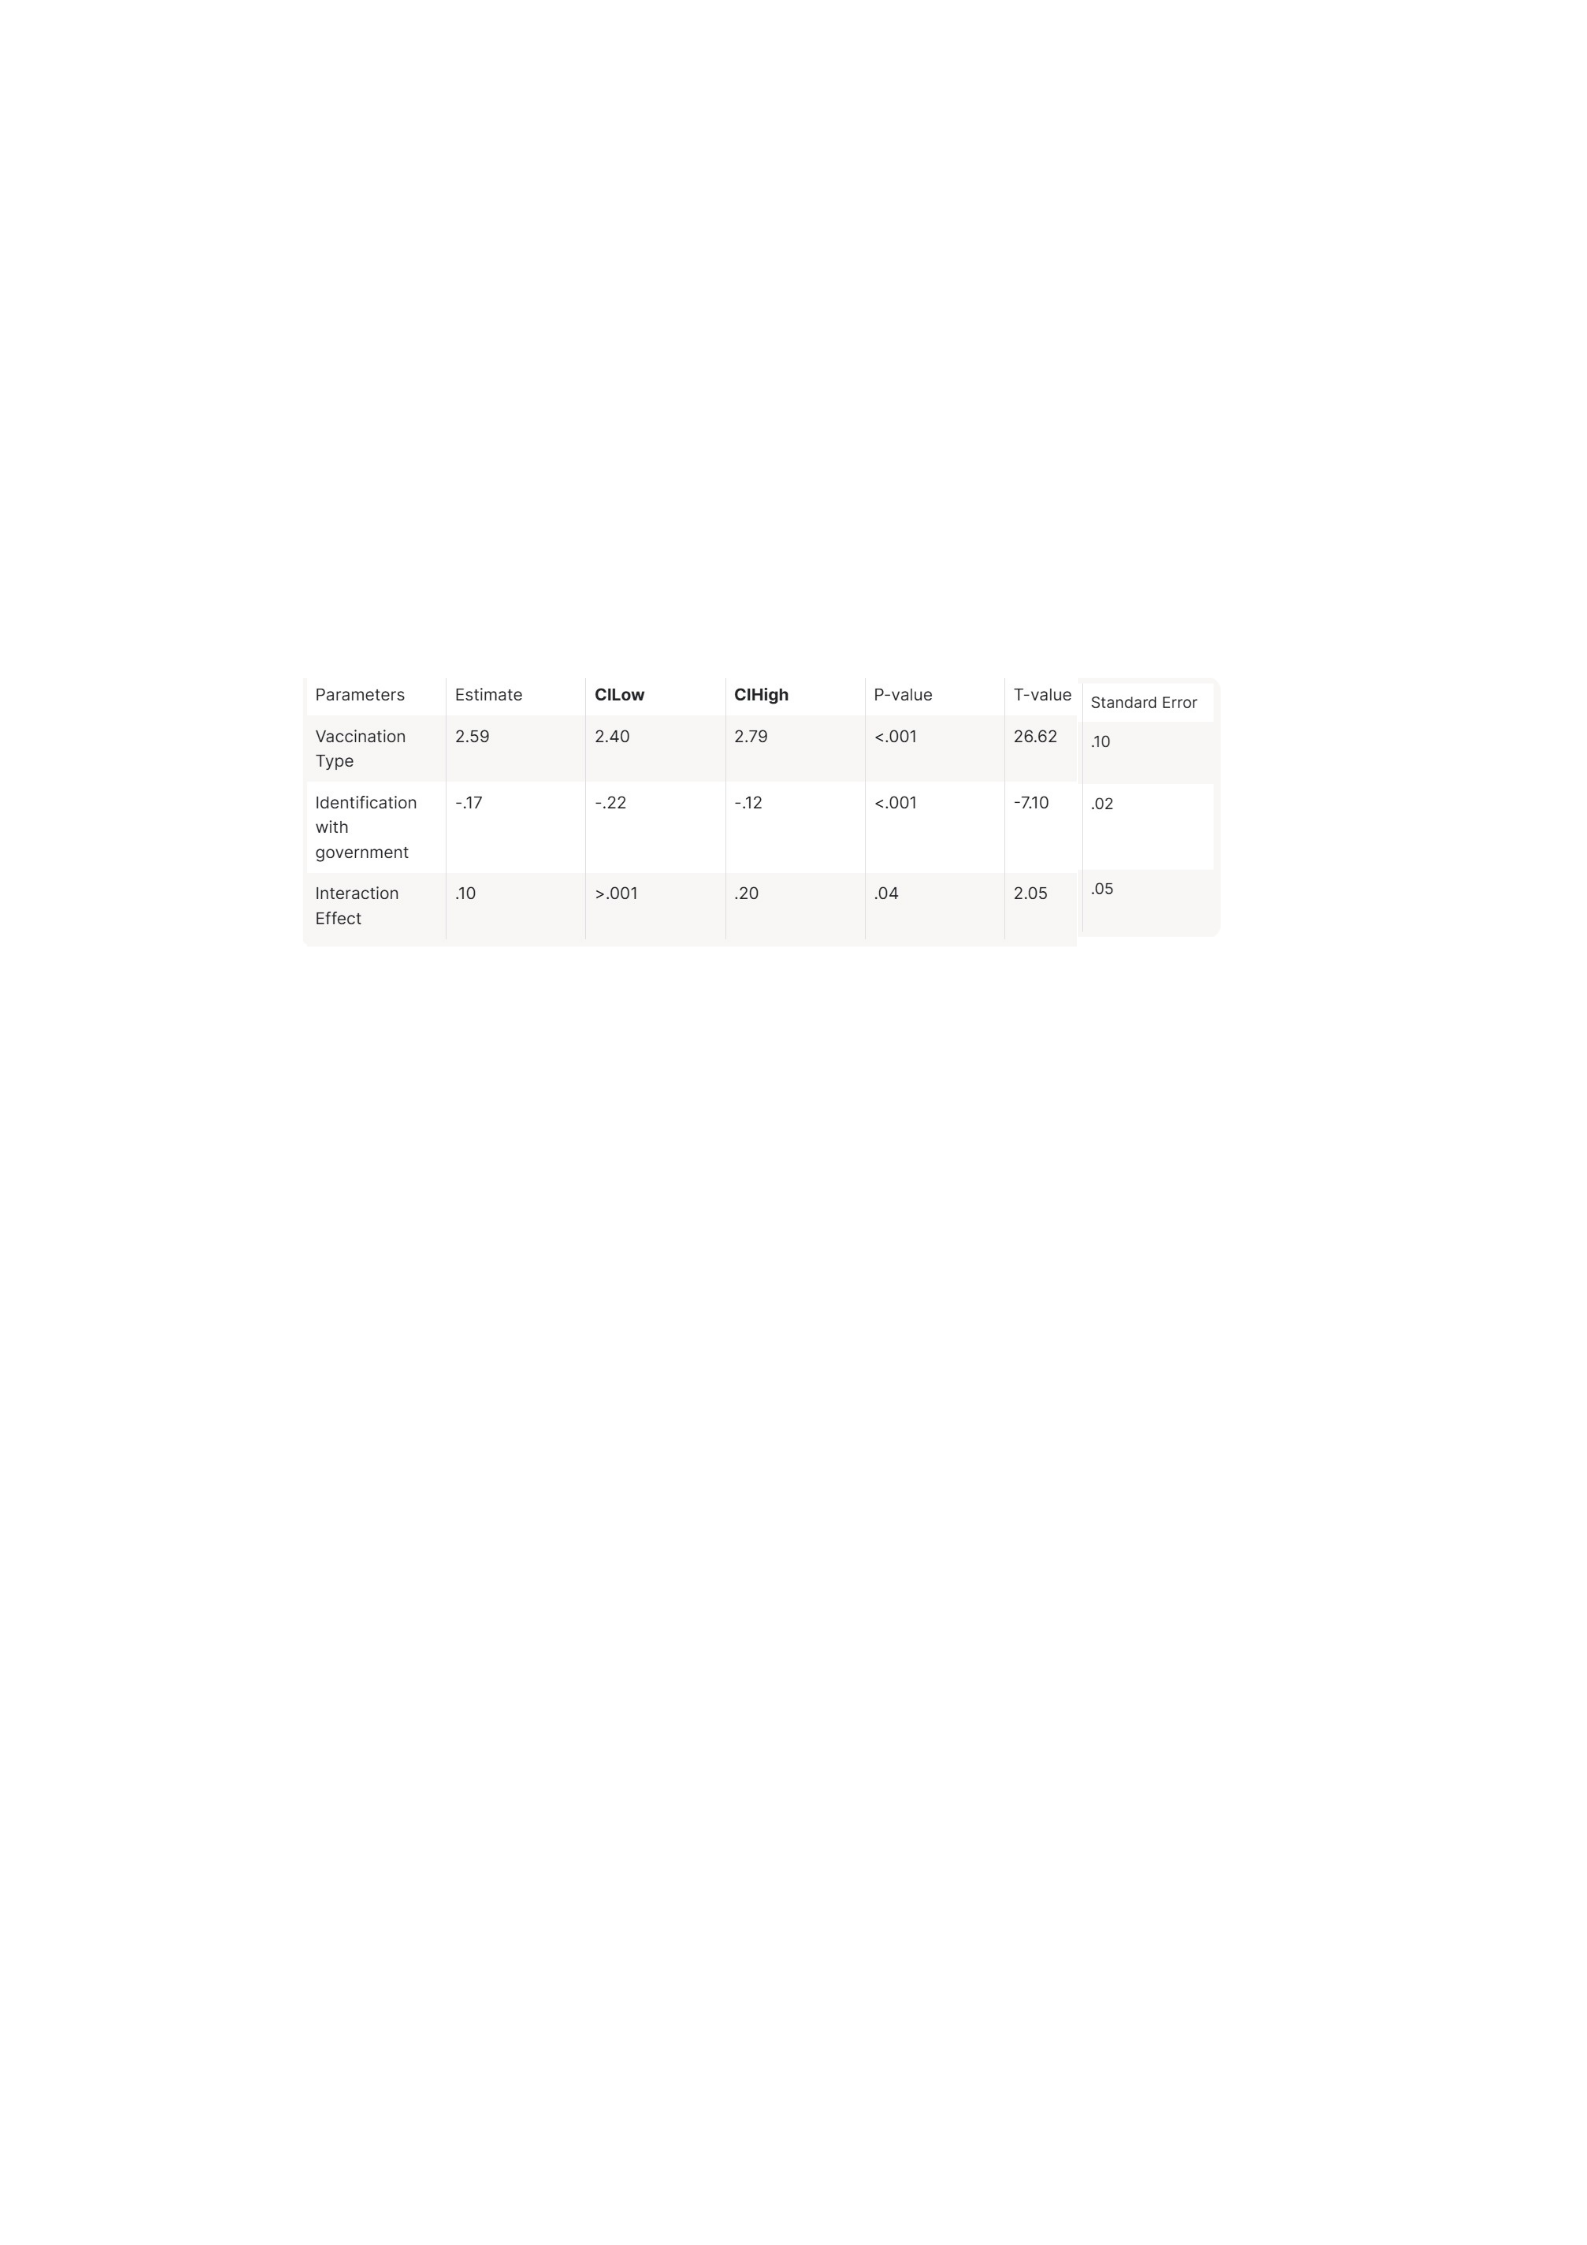
Table 3. Relationship between compulsion and anger moderated by
identification
The interactive effect between Vaccination type and Identification
issignificant b = 0.1, 95% CI [0.00, 0.20], t = -2.05, p =.04.The
confidence interval did not across zero, indicating that the relationship
between anger level and the type of vaccination ismoderated
byidentification. The positive interaction effect means that anger level
increase along with the increase of identification level. When people
identify more with the government, they are more agitated when they
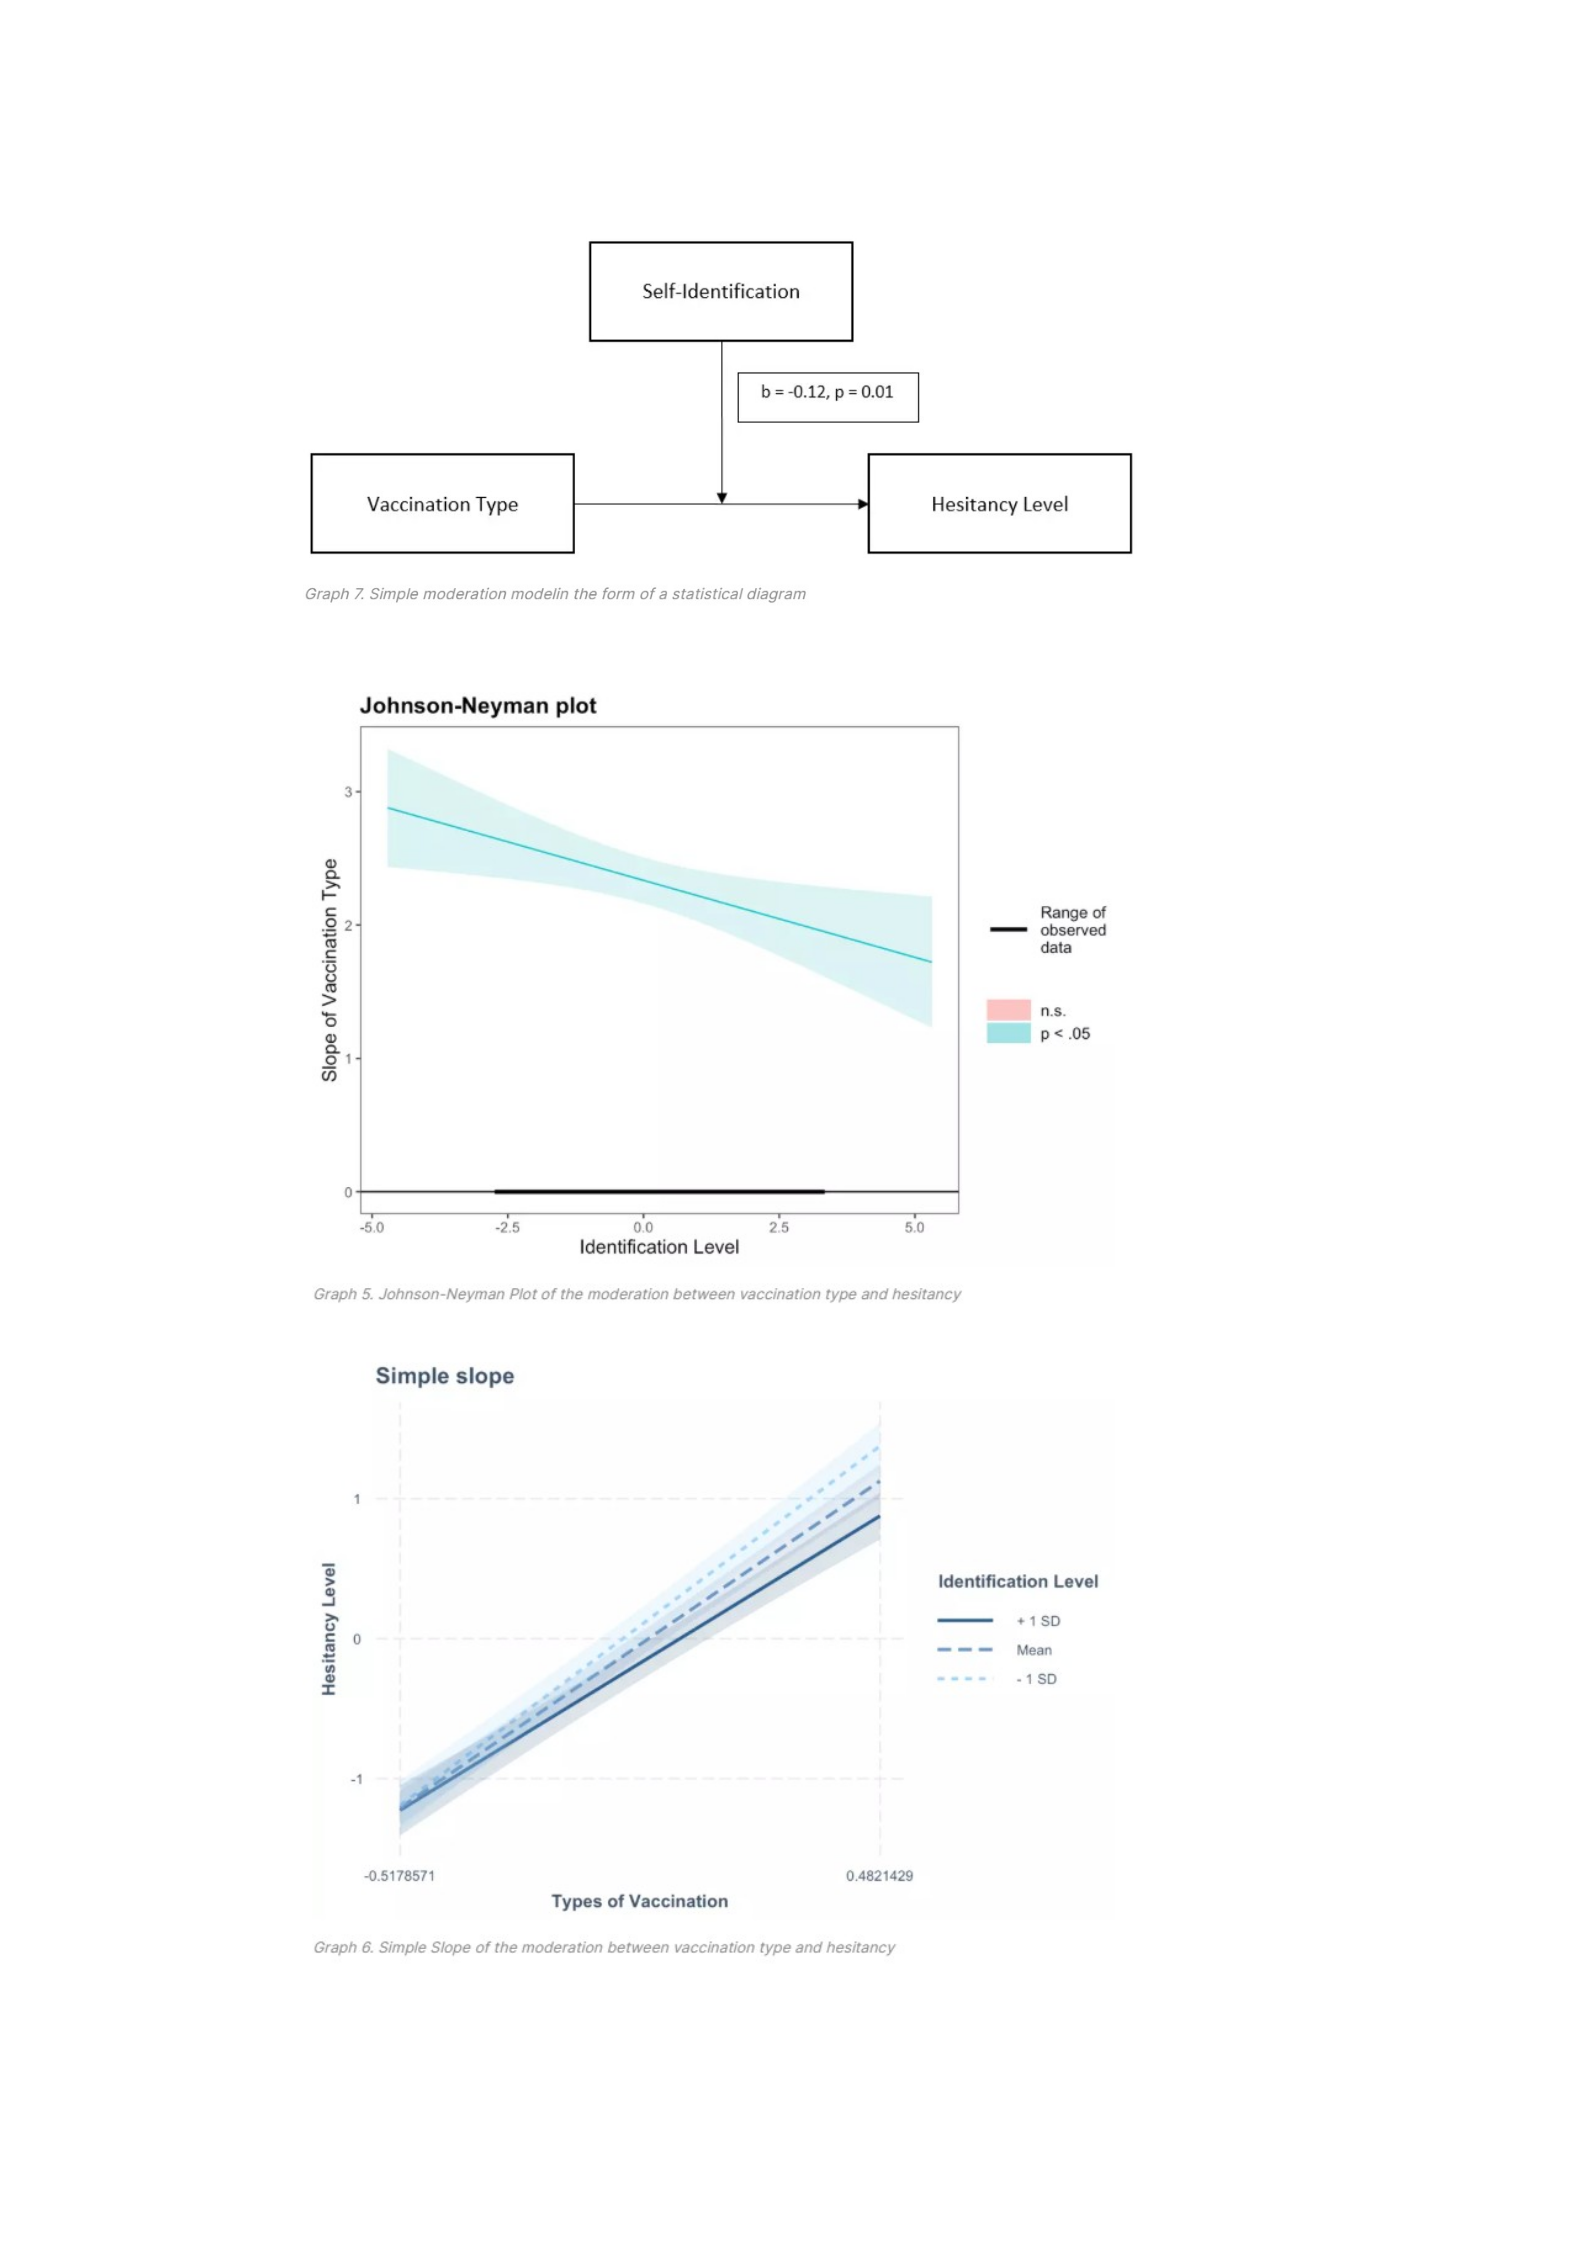
are forced to get vaccinated. According to the Johnson-Neyman plot,
the effect is significant across all different Identification level.In the
simple slopes results,lowIdentification level (-1 SD) b = 2.39, t =
17.28, p < 0.01, mean level b = 2.59, t = 26.6, p < 0.01 and high level
(+1 SD) b = 2.79, t = 20.19, p < 0.01, the type of vaccination is
significantly related to the anger from low to high level.
Mediation
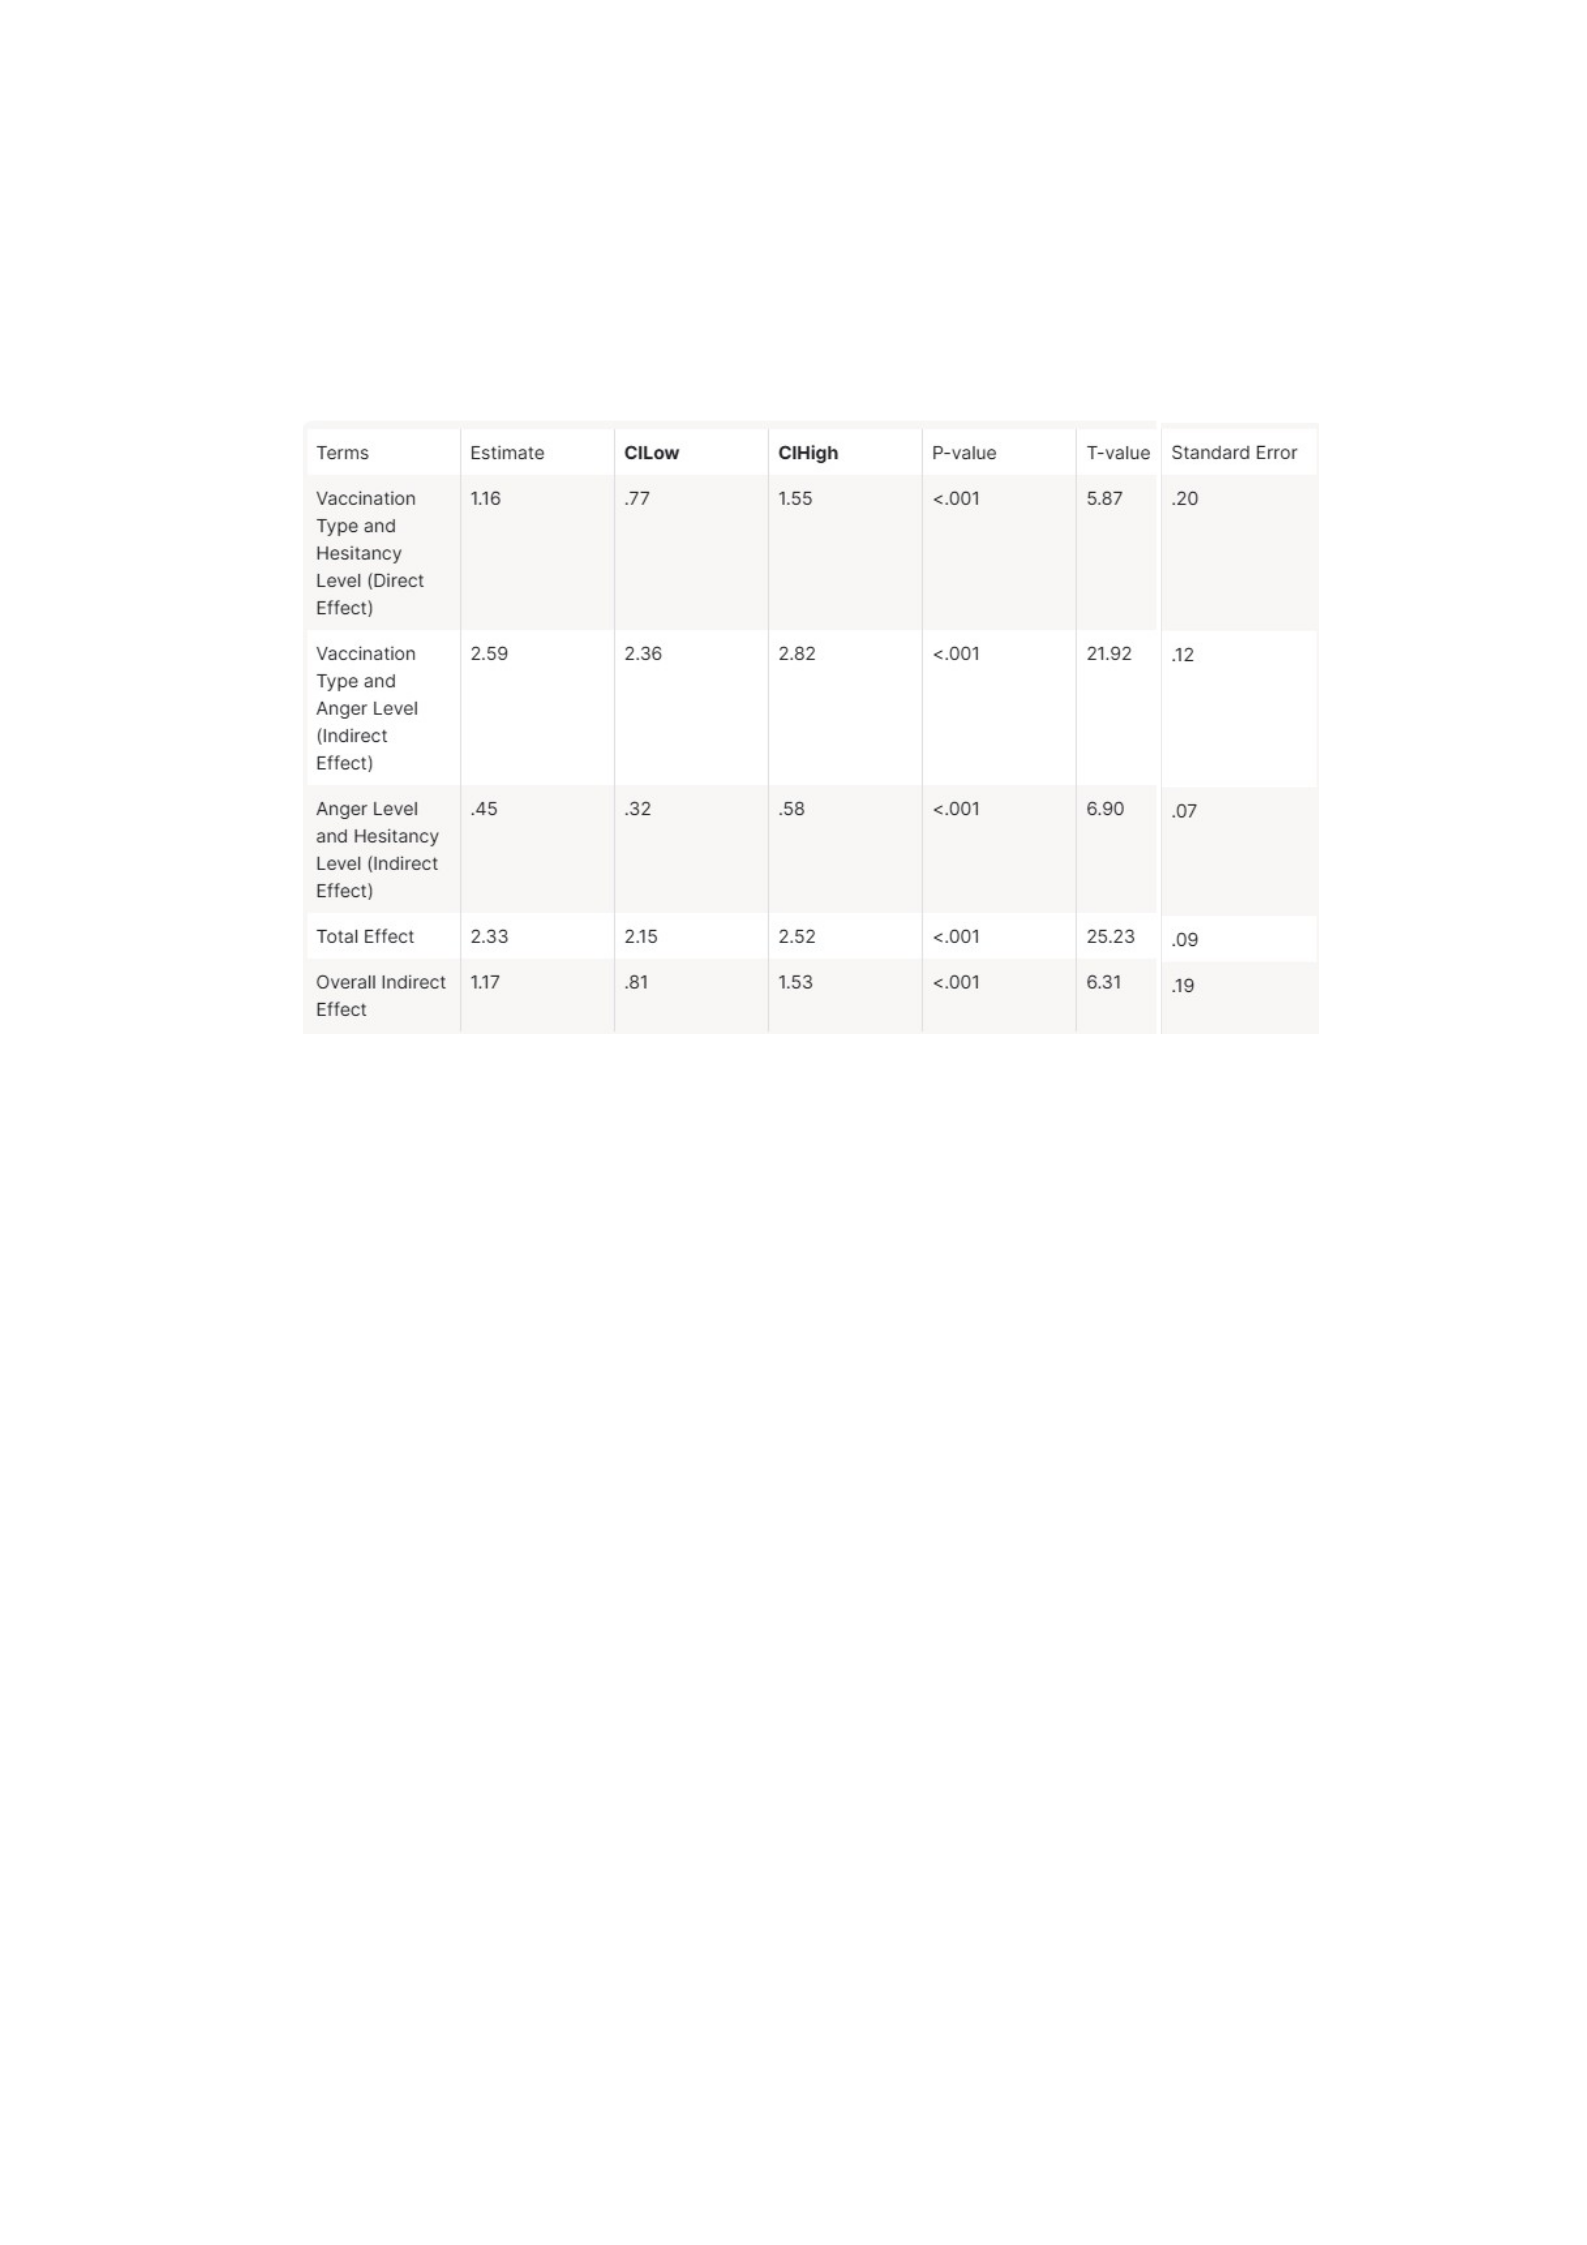
Table 6. Relationship between the type of vaccination and hesitancy
mediated by compulsion
In term of the fitting of the model, missing data were handled using
maximum likelihood and the number of observations is the same as
the number of original observations, thus none were excluded, and
bootstrapping was also used. Refers to the mediation equation, the
direct effect is b = 1.16, 95% CI [0.77, 1.55], t = 5.87, p < 0.001; the
effect of mediator (Anger Level) predicted from predictor
(Vaccination Type) is b = 2.60, 95% CI [2.36, 2.82], t = 21.92, p <
0.001; the relationship between the mediator and the outcome
(Hesitancy Level) is b = 0.45, 95% CI [0.32, 0.58], t = 6.90, p <
0.001; the total effect of predictor on the outcome is b = 2.33, 95% CI
[2.15, 2.52], t = 25.23, p < 0.001; the overall indirect effect of the
vaccination type (predictor) on hesitancy (outcome) via the
relationship of anger level (mediator) is b = 1.17, 95% CI [0.81, 1.53],
t = 6.31, p < 0.001. In general, compulsory vaccination predicts higher
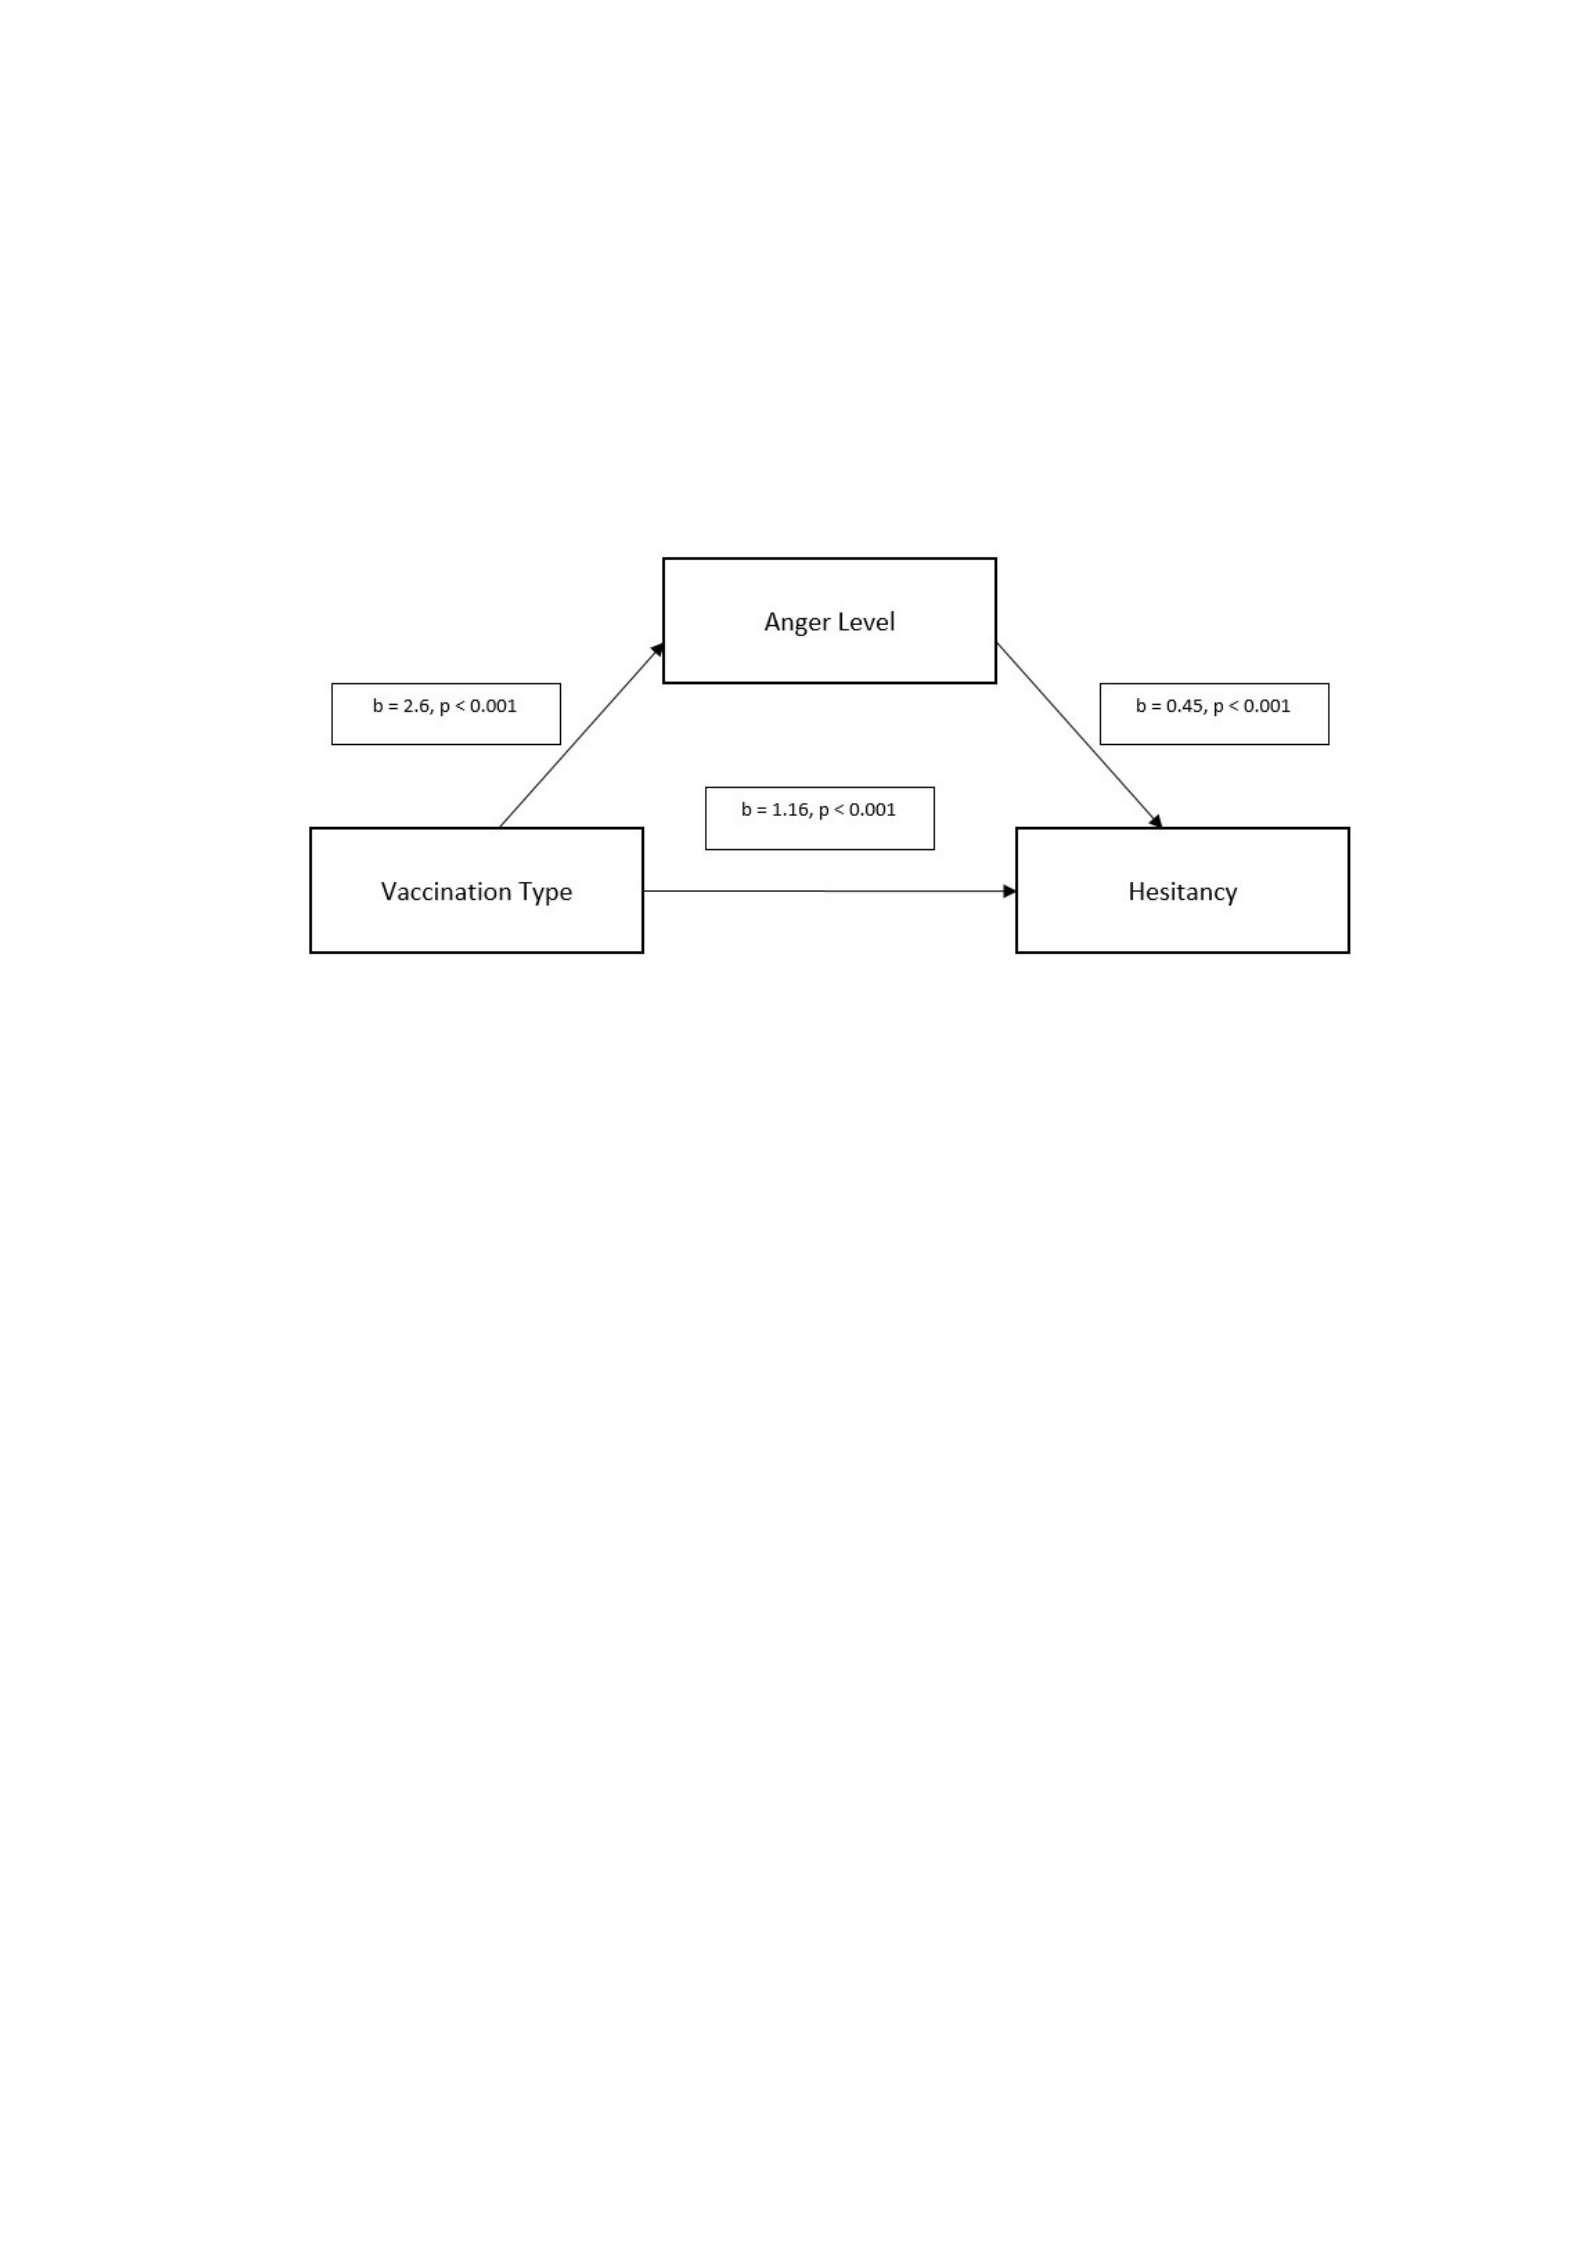
vaccine hesitancy because compulsory vaccination predicts increased
anger level, which predicts higher hesitancy towards vaccine uptake.
Anger level mediates the relationship between vaccination type and
hesitancy level, thanks to the significant indirect effect = 1.17, 95%
bootstrapped CIs [0.81, 1.53], and which does not includes 0.
Graph 8. Simple mediation modelin the form of a statistical diagram
Discussion
The purpose of the thesis was to establish the truth of the hypotheses
concerning voluntary or compulsory vaccination, considering the
variables of anger and identification with the government. A
significant finding is that positive identification with the government
increases rather than decreases the level of outrage when coercive
measures are introduced. Thus, individuals who have experienced
high levels of trust in government may lose it or become more hostile
toward politicians who campaign against their will. People do not
perceive all the government’s actions blindly, even if they have a
positive attitude towards it. On the contrary, they perceive the
vaccination itself much more harshly than those who did not initially
try to trust the government. The second and third hypotheses were
confirmed in the course of the study. They suggest that when people

identify negatively with the government, a mandatory vaccination
program increases hesitancy to use the vaccine. At the same time, the
effects of hesitancy decrease for those citizens who identify with the
government.
Vaccine safety conveys a lot of public attention, and it has numerous
grounds. When situations arise where adverse events are wrongly or
adequately attributed to vaccines, they can undermine confidence in
vaccines and the official bodies administering them (Machingaidze &
Wiysonge, 2021). This can ultimately become a significant cause of
numerous public health risks. The results of the vaccination campaign
and the rate have failed to stem the spread of the virus, and there have
been renewed calls to make vaccination compulsory everywhere
(Machingaidze & Wiysonge, 2021). Numerous governments have
refrained from this measure on the grounds of respecting the
fundamental rights and freedoms of their citizens. However, the
attitude toward the COVID-19 vaccine is a particular case: here, the
doubts are not due to anti-vaccination sentiments (Machingaidze &
Wiysonge, 2021). People most often explain their reluctance to be
immunized by the fact that they do not know about the side effects of
the vaccine and are unsure of its effectiveness.
COVID-19 vaccination is voluntary in most countries, but in order to
influence the category of unvaccinated, some countries have
introduced several measures that make life without vaccination
uncomfortable. For example, by banning the unvaccinated from public
places, requiring them to wear a mask and social distance once these
restrictions are lifted for the vaccinated, and introducing quarantines

for tourists without vaccination certificates. Several countries have
already imposed a mandatory vaccination requirement on specific
categories of the population (Murphy et al., 2021). Another incentive
could be the threat of losing one’s job. Furthermore, with the
introduction of compulsory vaccination coverage, vaccination
coverage rose by a third. In the CIS countries, the percentage who had
received at least one dose of vaccine increased 1.5-fold to 18% in
three weeks by July 6 (Murphy et al., 2021). Mandatory vaccination,
including vaccination against COVID-19, can be justified ethically if
the threat to public health is significant, confidence in the safety and
effectiveness of the vaccine is high, and the expected benefits of
mandatory vaccination exceed the alternative solutions.
The population of several countries also supports compulsory
vaccination against COVID-19. For example, three-quarters of
Australians support introducing such a requirement for workers,
students, and travelers. Moreover, the mandatory introduction of
vaccination would be supported by half of Belgians, half of the
managers of British firms, almost 70% of the Brazilian population,
and over 60% of residents of South Korea, Spain, China, and Italy
(Puri et al., 2020). At the same time, the study results conclude that
there is a clear difference between compulsory and voluntary
vaccination in terms of hesitancy to vaccinate. Voluntary vaccination
is perceived more acceptably and positively than mandatory
immunization.
Therefore, it is conceivable that the administrative costs of coercive
influence may be too significant, and it may exacerbate anti-

vaccination attitudes. Counterproductive can be another, softer form
of persuasion – limiting the access of unvaccinated people to specific
activities that are not vital, the researcher adds (Sallam, 2021). This
could be perceived as discrimination, especially while the vaccine is
difficult to obtain. In addition, such a measure would require a whole
list of exemptions and certainly does not promote a positive narrative
about the pro-social effects of vaccination.
First, if individuals are convinced that they do not need the vaccine,
the need to be vaccinated to continue working will, in some cases,
cause them to quit rather than get vaccinated. Second, penalties for
violating such requirements, such as fines, hit the least protected and
lowest-income populations (Salali & Uysal, 2020). In general,
mandatory vaccination predicts greater hesitancy to vaccinate because
mandatory vaccination predicts higher levels of anger, which signifies
greater reluctance. The level of rage mediates the relationship between
the type of vaccination and the level of indecision through a
significant indirect effect.
Correspondingly, people’s willingness to be vaccinated is closely
related to the level of trust in the authorities. The most painful effect
of harsh measures is the reduction of this confidence. Compulsory
vaccination signals that the rules do not trust society, provoking a
similar reaction (Sasaki et al., 2022). Firstly, the imposition of a
requirement for mandatory vaccination induces what is known as
psychic reactivity, that is, resistance associated with the individual’s
desire to maintain personal freedom of choice. Secondly, such a

decision leads to a moral disconnect between the individual and those
who force him to take specific actions.
If voluntary vaccination stimulates members of society to unite –
many are inclined to show themselves to be responsible citizens in
such a situation – then coercion leads to the opposite effect. The third
reason is decreased intrinsic motivation: pressure undermines trust in
both the authorities and other community members (Sasaki et al.,
2022). If the authorities force vaccination, other members of society
refuse to be vaccinated, which increases the resistance to vaccination
in general. Moreover, this effect also works for law-abiding citizens
who plan to be vaccinated voluntarily.
The conducted interviews suggest that people’s reactions to coercion
differ depending on their experience of living in a democratic or
authoritarian regime. Finding the reason for the rejection of vaccines
in a particular country or community would require a careful
examination of the local culture and political structure. Still, the main
issue in any vaccination campaign is one of trust. A vaccination
campaign must be based on trust between those who offer vaccines
and those who receive them (Troiano & Nardi, 2021). If it does not, it
becomes a struggle, and then it is challenging to keep the spread of the
disease under control. In principle, there will always be a proportion
of people in society who cannot be convinced to get vaccinated.
People need to be motivated to get vaccinated, explain what it gives,
what it protects against, and explain what to expect.

Moreover, the type of vaccination, the level of anger, and the level of
indecision have a positive relationship. Still, identification has no ties
to vaccination type, anger level, and indecisiveness. Vaccination
attitudes have a strong influence on vaccination decisions (Sok &
Fischer, 2020). Strong attitudes can take over-informed opinion and
the decision-making process. They can arise because of a particular
identity (religious, anthroposophical, or other), a lack of trust in the
appropriate governing bodies, or other factors. Social norms influence
individual intentions and attitudes about vaccination in various ways.
They subdivide the rules in the group, which determine the position,
as they describe how one person should behave or how most people
should behave. In this case, a group can be defined by where people
live, but it can also be determined by age, gender, socioeconomic
status, education, profession, religion, or other beliefs (Sok & Fischer,
2020). That is why a group can be an ethnic group, a specific urban
neighborhood, or an online anti-vaccine group.
Both the belief that others think one should be vaccinated and the fact
that others are vaccinated can influence your stance on vaccination.
Group members tend to conform to the majority position. Thus, when
vaccination in a group increases, other members tend to be inclined to
get vaccinated. Norms can also be counterproductive, where the social
example in a community is not to get immunized (Troiano & Nardi,
2021). Belonging to a group that shares particular religious,
educational, philosophical, or other views can also influence one’s
stance on vaccination.

When a group’s norms do not support vaccination, its members will
refrain from immunization in order to preserve their identity and
belonging to the group. Culture influences attitudes and risk
awareness in the same way that it influences willingness to participate
in community activities (e.g., contributing to collective immunity) and
approval of governing bodies. It should be noted that culture is not
static; it is pretty fluid. Global networks and global social connections
have an enormous impact on culture – it no longer belongs to a
specific country. Global online user communities opposed to
vaccination are an example of this. Concerns about vaccine safety
represent a situation in which adverse events are rightly or wrongly
associated with vaccination and create a sense of danger and lack of
trust in vaccination and health authorities.
Distrust of vaccination and concerns about vaccine safety are
interrelated. When mistrust of vaccines is high, populations are more
easily exposed to misperceptions about vaccines. Concerns about
vaccine safety in a number of countries have increased distrust of
vaccination, as demonstrated by decreased confidence in vaccination
and health authorities (Wilson & Wiysonge, 2020). This means that
addressing mistrust of vaccination is essential not only to increase
vaccination coverage but also to ensure that the public is held firm
against concerns about vaccine safety. It also implies that an effective
response to vaccine safety concerns can help prevent the escalation of
public distrust of vaccination. Coercive measures would temporarily
raise the vaccination rate, adding another 10-15% to the current level
(Troiano & Nardi, 2021). Simple administrative coercion will save the
management system from stupor and the search for complicated

moves. However, it will be risky to increase the pressure further
because of the Duma campaign, and after the elections, other
circumstances may change. Therefore, vaccination is likely to be
mandatory but highly inconsistent.
However, sometimes, in the public interest, in the desire of protecting
the vast majority of the population, these kinds of decisions can also
be generally compulsory. In this case, the balance between
voluntariness and obligation can be reversed in favor of commitment.
Even though, according to the World Health Organization (WHO),
vaccination saves 4 to 5 million lives worldwide each year (Wilson &
Wiysonge, 2020). No preventive intervention, including hygiene and
sanitation, the use of antibiotics, mammograms, and colonoscopies,
has proven as effective in preventing disease as the use of vaccines.
Vaccination, however, requires an earnest collective effort and the
close cooperation of citizens with health workers. Nevertheless, many
people in today’s world distrust having their health issues handled by
the government. When people identify less with the government, they
are more likely to hesitate against vaccination when it is mandatory.
However, it should be noted that the study may be inaccurate because
the efficacy and stimulus of the vaccine are not taken into account.
Different types of vaccines have other effects on the human body,
adverse reactions, and hence determination. Considering these
indicators together with the study already conducted may be a valid
topic for further research. Establishing a correlation between the type
of vaccine and its stimuli might show changes in people’s

determination in more detail. In this way, an accurate conclusion can
be drawn about how voluntary or compulsory vaccination affects
choice. It would also be interesting to determine whether the level of
anger decreases when vaccinated with a particular type of drug whose
effectiveness has been most widely confirmed.
Conclusion
Vaccination is the most reliable way to control infectious disease or
weaken its course. It is a typical preventive procedure, a thoroughly
controlled process, the reaction to which is comprehended to doctors
and is entirely predictable. Nevertheless, the coronavirus infection
forced a changed attitude toward vaccination among the population,
distrustful of previously untested medicines. It was found that there is
a clear difference between compulsory and voluntary vaccination in
terms of hesitancy to immunize. Applying a Pearson graph, it was
possible to display an overview of the relationship between each
variable taken. It demonstrated that only vaccination type, level of
anger, and indecisiveness had a positive relationship. On the other
hand, identification has no connection with vaccination variety,
irritation level, or grade of uncertainty. Moreover, it is revealed that
when people identify more with the government, they feel more
annoyed when forced to vaccinate. When individuals place less with
the government, they are more conceivable to hesitate against
vaccination when it is mandatory. Furthermore, compulsory
vaccination predicts greater hesitancy to vaccinate because mandatory
immunization predicts higher levels of anger.
Everyone should have the freedom to manage his or her own body and
health independently. When the state starts to adopt the principle of

the forcible provision of a good, it is out of the realm of health care.
Suppression, coercion, violence are not about medicine or health, nor
about notorious rights and liberties. They raise a question about
whether there is the liberty of choice, conscience, and decision-
making. The government often stands up for freedom of opinion
during the election period, trying to fill the polling stations as much as
possible. After all, officials often provide citizens with violent
interference with their health. Those measures immediately provoke a
reaction of anger, and as the study demonstrated, people who identify
with the government have an even more negative perception of
coercive measures. Irritation and identification correlate directly with
determination about vaccines. Voluntary immunization is sufficiently
received by the population and does not contradict the rights of
citizens, so it is a program that should be present in every democracy.

References
Anderson, R. M., Vegvari, C., Truscott, J., & Collyer, B. S. (2020).
Challenges in creating herd immunity to SARS-CoV-2 infection by
mass vaccination. The Lancet, 396(10263), 1614-1616.
Cislak, A., Marchlewska, M., Wojcik, A. D., Śliwiński, K., Molenda,
Z., Szczepańska, D., & Cichocka, A. (2021). National narcissism and
support for voluntary vaccination policy: The mediating role of
vaccination conspiracy beliefs.Group Processes & Intergroup
Relations, 24(5), 701-719.
Craig, B. M. (2021). United States COVID-19 vaccination preferences
(CVP): 2020 hindsight. The Patient-Patient-Centered Outcomes
Research, 14(3), 309-318.
D’Ancona, F., D’Amario, C., Maraglino, F., Rezza, G., & Iannazzo, S.
(2019). The law on compulsory vaccination in Italy: an update 2 years
after the introduction. Eurosurveillance, 24(26), 1900371.
Dillard, J. P., & Shen, L. (2005). On the nature of reactance and its
role in persuasive health communication. Communication
monographs, 72(2), 144-168.

Dror, A. A., Eisenbach, N., Taiber, S., Morozov, N. G., Mizrachi, M.,
Zigron, A., & Sela, E. (2020). Vaccine hesitancy: the next challenge
in the fight against COVID-19.European journal of epidemiology,
35(8), 775-779.
Freeman, D., Loe, B. S., Chadwick, A., Vaccari, C., Waite, F.,
Rosebrock, L., & Lambe, S. (2020). COVID-19 vaccine hesitancy in
the UK: the Oxford coronavirus explanations, attitudes, and narratives
survey (Oceans) II. Psychological medicine, 1-15.
doi:10.1017/S0033291720005188
Feng, X., Wu, B., & Wang, L. (2018). Voluntary vaccination dilemma
with evolving psychological perceptions.Journal of Theoretical
Biology, 439, 65-75.
Giubilini, A. (2020). An argument for compulsory vaccination: the
taxation analogy. Journal of applied philosophy, 37(3), 446-466.
Glenn, G. M., & Kenney, R. T. (2018). Mass vaccination: solutions in
the skin.Mass vaccination: global aspects—progress and obstacles,
247-268.
Goralnick, E., Kaufmann, C., & Gawande, A. A. (2021). Mass-
vaccination sites—an essential innovation to curb the Covid-19
pandemic. New England Journal of Medicine, 384(18), 67. doi:
10.1056/NEJMp2102535

Gualano, M. R., Olivero, E., Voglino, G., Corezzi, M., Rossello, P.,
Vicentini, C., & Siliquini, R. (2019). Knowledge, attitudes and beliefs
towards compulsory vaccination: a systematic review.Human
Vaccines & Immunotherapeutics, 15(4), 918-931.
Han, J., Cha, M., & Lee, W. (2020). Anger contributes to the spread of
COVID-19 misinformation.Harvard Kennedy School Misinformation
Review, 1(3).
Hasan, T., Beardsley, J., Marais, B. J., Nguyen, T. A., & Fox, G. J.
(2021). The implementation of mass-vaccination against SARS-CoV-
2: a systematic review of existing strategies and guidelines. Vaccines,
9(4), 326.
Hosangadi, D., Warmbrod, K. L., Martin, E. K., Adalja, A., Cicero,
A., Inglesby, T., & Connell, N. (2020). Enabling emergency mass
vaccination: innovations in manufacturing and administration during a
pandemic. Vaccine, 38(26), 4167. doi: 10.1016/j.vaccine.2020.04.037
Davis, C. J., Golding, M., & McKay, R. (2021). Efficacy information
influences intention to take COVID‐19 vaccine. British Journal of
Health Psychology, 2(1), 22-23.
Graeber, D., Schmidt-Petri, C., & Schröder, C. (2021). Attitudes on
voluntary and mandatory vaccination against COVID-19: Evidence
from Germany. PloS one, 16(5), 23-34.

Jennings, W., Stoker, G., Willis, H., Valgardsson, V., Gaskell, J.,
Devine, D., & Mills, M. C. (2021). Lack of trust and social media
echo chambers predict COVID-19 vaccine hesitancy. MedRxiv, 2021-
01.
Kerr, J. R., Freeman, A. L., Marteau, T. M., & van der Linden, S.
(2021). Effect of information about COVID-19 vaccine effectiveness
and side effects on behavioural intentions: two online
experiments.Vaccines, 9(4), 379.
Krasser, A. (2021). Compulsory vaccination in a fundamental rights
perspective: Lessons from the ECtHR. ICL Journal, 15(2), 207-233.
Leach, C. W., Van Zomeren, M., Zebel, S., Vliek, M. L., Pennekamp,
S. F., Doosje, B., & Spears, R. (2008). Group-level self-definition and
self-investment: a hierarchical (multicomponent) model of in-group
identification.Journal of personality and social psychology, 95(1),
144.
Lucia, V. C., Kelekar, A., & Afonso, N. M. (2021). COVID-19
vaccine hesitancy among medical students. Journal of Public Health,
43(3), 445-449.
Machingaidze, S., & Wiysonge, C. S. (2021). Understanding COVID-
19 vaccine hesitancy.Nature Medicine, 27(8), 1338-1339.

Mills, M. C., & Rüttenauer, T. (2022). The effect of mandatory
COVID-19 certificates on vaccine uptake: synthetic-control modelling
of six countries. The Lancet Public Health, 7(1), 15-22.
Motta, M., Sylvester, S., Callaghan, T., & Lunz-Trujillo, K. (2021).
Encouraging COVID-19 vaccine uptake through effective health
communication. Frontiers in Political Science, 3, 1.
Murphy, J., Vallières, F., Bentall, R. P., Shevlin, M., McBride, O.,
Hartman, T. K., & Hyland, P. (2021). Psychological characteristics
associated with COVID-19 vaccine hesitancy and resistance in Ireland
and the United Kingdom.Nature communications, 12(1), 1-15.
Neumann-Böhme, S., Varghese, N. E., Sabat, I., Barros, P. P.,
Brouwer, W., van Exel, J., & Stargardt, T. (2020). Once we have it,
will we use it? A European survey on willingness to be vaccinated
against COVID-19. The European Journal of Health Economics,
21(7), 977-982.
Palm, R., Bolsen, T., & Kingsland, J. T. (2021). The effect of frames
on COVID-19 vaccine resistance. Frontiers in Political Science, 3, 41.
Puri, N., Coomes, E. A., Haghbayan, H., & Gunaratne, K. (2020).
Social media and vaccine hesitancy: new updates for the era of
COVID-19 and globalized infectious diseases. Human vaccines &
immunotherapeutics, 16(11), 2586-2593.

Renström, E. A., & Bäck, H. (2021). Emotions during the Covid‐19
pandemic: Fear, anxiety, and anger as mediators between threats and
policy support and political actions.Journal of Applied Social
Psychology, 51(8), 861-877.
Robertson, E., Reeve, K. S., Niedzwiedz, C. L., Moore, J., Blake, M.,
Green, M., & Benzeval, M. J. (2021). Predictors of COVID-19
vaccine hesitancy in the UK household longitudinal study.Brain,
behavior, and immunity, 94, 41-50.
Sittenthaler, S., Traut-Mattausch, E., Steindl, C., & Jonas, E. (2015).
Salzburger state reactance scale (SSR Scale). Zeitschrift für
Psychologie.
Savulescu, J. (2021). Good reasons to vaccinate: mandatory or
payment for risk?. Journal of medical ethics, 47(2), 78-85.
Sallam, M. (2021). COVID-19 vaccine hesitancy worldwide: a
concise systematic review of vaccine acceptance rates.Vaccines, 9(2),
160.
Salali, G. D., & Uysal, M. S. (2020). COVID-19 vaccine hesitancy is
associated with beliefs on the origin of the novel coronavirus in the
UK and Turkey. Psychological medicine, 1-3.
doi:10.1017/S0033291720004067

Sasaki, S., Saito, T., & Ohtake, F. (2022). Nudges for COVID-19
voluntary vaccination: How to explain peer information?Social
Science & Medicine, 292, 114561.
Savulescu, J., Giubilini, A., & Danchin, M. (2021). Global ethical
considerations regarding mandatory vaccination in children. The
Journal of Pediatrics, 231, 10-16.
Sherman, S. M., Smith, L. E., Sim, J., Amlôt, R., Cutts, M., Dasch, H.,
& Sevdalis, N. (2021). COVID-19 vaccination intention in the UK:
results from the COVID-19 vaccination acceptability study
(CoVAccS), a nationally representative cross-sectional survey. Human
vaccines & immunotherapeutics, 17(6), 1612-1621.
Sinclair, S., & Agerström, J. (2021). Do social norms influence young
people’s willingness to take the COVID-19 vaccine?. Health
Communication, 1-8.
Smith, L. E., Duffy, B., Moxham-Hall, V., Strang, L., Wessely, S., &
Rubin, G. J. (2021). Anger and confrontation during the COVID-19
pandemic: a national cross-sectional survey in the UK. Journal of the
Royal Society of Medicine, 114(2), 77-90. doi:
10.1177/0141076820962068
Sok, J., & Fischer, E. A. (2020). Farmers’ heterogeneous motives,
voluntary vaccination and disease spread: an agent-based
model.European Review of Agricultural Economics, 47(3), 1201-
1222.

Sprengholz, P., Eitze, S., Felgendreff, L., Korn, L., & Betsch, C.
(2021). Money is not everything: experimental evidence that
payments do not increase willingness to be vaccinated against
COVID-19. Journal of Medical Ethics, 47(8), 547-548.
Troiano, G., & Nardi, A. (2021). Vaccine hesitancy in the era of
COVID-19. Public health, 194, 245-251.
Wilson, S. L., & Wiysonge, C. (2020). Social media and vaccine
hesitancy. BMJ Global Health, 5(10), 4206-4209.

