


1
POLICY OUTCOMES OF CULTURALLY INTEGRATED HEALTH CARE FOR AFRICAN
AMERICANS
Chapter 1: Introduction to the Study
Health care policy in the United States has been lacking for quite some time; more
specifically, there is a lack of policy that addresses institutional and systematic racial influences
that have directly contributed to the inequitable system of care that continues to undermine the
current health care climate in the United States. As a result, disenfranchised and marginalized
groups have been victims of inequitable health care delivery. Most notably, African Americans
suffer more chronic diseases than their White counterparts and are also 40% more likely to die
from a treatable condition (Cunningham et al., 2017). These numbers increase when compounded
with a behavioral health diagnosis (Blue Cross Blue Shield Association, 2022). Thus, mortality
rates for this group are exponentially higher than any other race group. Many factors contribute
to the combined incumbrance of chronic disease and medical conditions among individuals with
behavioral health diagnoses, such as the inability to adequately provide self-care, lifestyle
choices, effects of medication use, and, most notably, socioeconomic influences (Scharf et al.,
2014).
On the matter of policy, the United States had been slow to enact a policy that addressed
both the implicit and explicit influences of racism and privilege in health policy as it relates to
high-quality, equitable access for all citizens up until 2010, with the Patient Protection and
Affordable Care Act of 2010 (ACA). However, it still had its faults as it relates to affordable,
high quality, equitable care, such as limited access to providers, narrow networks thus limiting
choice, affordability concerns, poor quality of care, equity concerns for marginalized
communities and cost containment which impacted quality (Kaiser Family Foundation, 2021).

2
But in the meantime, there have been efforts to address these issues such as the National
Partnership for Action to end Health Disparities and the National Standards for Culturally and
Linguistically Appropriate Services, which both focus on addressing and reducing implicit bias in
health care and promoting equity (Office of Minority Health, 2021), there still lacks any actual
policy. While federal agencies such as the U.S. Department of Health and Human
Services (DHHS) and the Substance Abuse and Mental Health Services Administration
(SAMHSA) have advocated for the integration of primary care and behavioral health care, there
remains a lack of information on what is needed to help promote the consideration of social
determinants of health (SDoH) and the systematic policy disparities that play a role in the care of
African American patient’s care (Yearby, 2020).
SDoH is defined by the DHHS' Office of Disease Prevention and Health Promotion as
“the conditions in the environments where people are born, live, learn, work, play, worship, and
age that affect a wide range of health, functioning, and qualityof-life outcomes and risks.”
(Healthy People, 2020, para. 1). The SDoH are divided into five domains: (a) economic stability,
(b) education access and quality, (c) health care access and quality, (d) neighborhood and built
environment, and (e) social and community context (Centers for Disease Control and Prevention
(DHHS, 2020); but for the intended study, the domain of focus will be on health care access and
quality.
Efforts have been made to pass legislation aimed at addressing inequalities related to the
SDoH. Several bills are currently under consideration, such as the Social
Determinants of Health Act of 2020 (S.104/H.R. 379), the Social Determinants Accelerator Act
of 2021 (H.R. 2503), the Leveraging Integrated Networks in

3
Communities to Address Social Needs Act (S.509), and the Public Health Infrastructure
Saves Lives Act (S.674).
This qualitative study will contribute to the literature and knowledge on the problem and
prospects around health care policy by presenting the perspectives gathered from interviews of
African American patients receiving health care services from a federally qualified health center
(FQHC), in order to understand the interplay between the SDoH and the systemic policy
disparities that play a role in their health care. This chapter includes background information on
behavioral health and chronic care inequities with respect to African Americans and the benefits
of integrated care as it relates to SDoH. The research problem, purpose, and research questions
that guide the study are introduced and discussed. Followed by an overview of the conceptual
frameworks that ground the study and its application to the study. Next, an overview of the
nature of the study; assumptions, definitions, scope, delimitations, and limitations; and lastly the
significance of the study with regards to practice, theory, and social change.
Background of the Study
Integrated care in the United States can be traced back to the early 1980s. It was a
response to the fragmented care in the United States that, as a result of care by different
providers; gaps in access, quality, and efficiency of care, have resulted in high societal costs;
disabilities; excess mortalities; as well as fragmentation across governance actors (Druss &
Goldman, 2018). The Epidemiological Catchment Area Survey, conducted by the DHHS and the
National Institute of Mental Health (NIMH), took place between 1980 and 1985. Its purpose was
to gather data on the prevalence and incidence of mental disorders, as well as the need for
services among individuals with mental illness (DHHS & NIMH, 1994). The study was

4
implemented in very particular cities in very specific communities. The study yielded three
findings that would eventually have major effects on care integration. The findings revealed the
following:
• mental disorders were highly prevalent- more than a quarter of individuals had a
diagnosable mental disorder in a given year,
• fewer than half of the individuals with a diagnosis received treatment in any given
year, and
• those who did receive mental health treatment most commonly received it not from
specialty mental health providers but general practitioners .
The results proved an importance for not only treating mental health disorders, but doing so in a
primary care setting (Druss & Goldman, 2018).
The late 1980s and early 1990s brought on newer treatments and billing models that
interrupted the integration of primary care and mental health treatment (Druss & Goldman,
2018), such as rising health costs related to insurance benefits and treatment and general care
costs (Druss & Goldman, 2018). This period allowed for additional research on integrated care.
One study compared a comprehensive intervention for patients with depression to standard
primary care. The results showed that depressive symptoms improved over 30- and 90-day
periods when patients were treated with prescribed medication by primary care physicians(Katon
et al., 1995). Other studies also showed the same effectiveness in improving quality and
outcomes related to substance use disorders (Watkins et al., 2017) and managing patients with
chronic and severe mental illness (Druss et al., 2017).

5
By 1996, a health reform in many aspects of health care delivery began through
legislation that changed how we viewed insurance and care delivery. Before the ACA was passed,
there was an average of 12,000,000 individuals with mental health and substance use disorders
(Garfield et al., 2011). Those with insurance had separate and unequal behavioral health benefits
compared with general medical and surgical conditions. As a result of this, mental health
expenditures caused financial hardship for many people. As a result, the Mental Health Parity Act
of 1996 prohibited large group health plans that offer mental health benefits from imposing more
restrictive annual or lifetime limits on spending for mental illness than on coverage of physical
illness (Centers for Medicare & Medicaid Services (2023). However, by 2008, that would
advance to what is known as the Mental Health Parity and Addiction Equity Act, which provided
added protection in addition to the original law towards access to health insurance and reduction
of the financial burden for patients with mental illness and substance use by applying parity
requirements, baring differential coverage limits, but it did not mandate coverage (Chapman et
al., 2017; CMS, 2023; Druss & Goldman, 2018). Nevertheless, this advancement did reveal at
the time the benefits of integration.
The passing of the ACA in 2010 allowed for funding for common mental disorders in
primary care and medical issues in public sector mental health settings. These settings included
health homes or patient-centered medical homes, community mental health centers, community
behavioral health clinics, and so forth, for comprehensive care coordination, especially for
individuals with severe and chronic mental illnesses (Druss & Goldman, 2018). The ACA also
targeted integration, especially for Medicaid recipients. With this came new billing codes for

6
collaborative care, waivers for states (Sandhu et al., 2021) but more than that, it was the start of
integrated care in federal health policy.
Despite the potential the ACA had for integration delivery in health care, the benefits for
people of color (POC) seem to have fallen short. Research has demonstrated that POC are less
likely to receive treatment for mental health and/or substance use disorders, especially when they
have an added chronic disorder (Burkett, 2017). One reason for not receiving treatment is the
reluctance to seek treatment due to stigma, negative attitudes, and lack of culturally appropriate
treatment (Burkett, 2017). When POC do receive the treatment, they typically receive poor
quality care (Pinedo & Villattaro 2020). Moreover, the systemic and discriminatory racial
practices that POC have faced (McMorrow et al, 2021) have had a role in their physical health
status, and these inequities are quite observable and persistent throughout the course of life
(Wippold & Frary, 2021). While studies have shown that integrated behavioral health care has the
potential to improve symptoms and functions of co-occurring disorders as well as reduce stigma
in marginalized populations (O’Loughlin et al., 2019), there still remains the need for
improvement as it relates to engaging marginalized groups to continue investing into the
integrated model (Blackmore et al, 2022).
To date, there is insufficient research on the effects of the lack of policies concerning
culturally integrated behavioral health care (CIBHC) that recognizes and addresses the specific
SDoH that influence low health outcomes for African Americans. In order to understand this
problem and provide substantial solutions, this study will take into account lived experiences of
African American patients regarding their experience with their both their integrated behavioral

7
health care providers and the specific SDOH and cultural influences in their care approach that
affect their health outcomes.
Problem Statement
The problem of health inequalities and poor health outcomes for African Americans with
co-occurring health conditions, which contributes to low health outcomes and further contributes
to health inequality. This study will explore the lack of research on the administration of health
care policy on poor health care delivery in the United States as it relates to CIBHC. Current
studies revealed a significant number of health inequities as it relates to the African American
community, implementation of integrated care, and qualitative exploration of lived experiences
for marginalized groups generally; thus, revealing a gap in research regarding qualitative
exploration of lived experiences of African Americans. Also, the indicated need to research the
problem further, bring awareness for a culturally appropriate need to improve health outcomes,
create social change, influence policy, decrease and eventually eliminate health disparities and
establish policy that will influence an improved architype of health care delivery that will benefit
not just African Americans but all marginalized groups. Studies have not sought to explore the
influence of both institutional and systemic policies on the SDoH and the role they play in
African Americans care, which attribute to low health outcomes. Thus the research problem that
will be addressed in in this qualitative study will be health inequalities as it relates to African
American Americans and the implementation of CIBHC as a response improving health care
access and quality and overall health outcomes.

8
Purpose of the Study
The purpose of this qualitative study is to understand the implementation of CIBHC as it
relates to the African Americans experience while taking into consideration health care access
and quality (SDoH), from a public policy lens. Considering the African American community’s
relationship with health care institutions, integrated care with all its advancements continues to
be an unintended divesture for African Americans (Blackmore et al, 2022). As it relates to
CIBHC, the intersection of health care access and quality and its effects on health outcomes; by
presenting lived experiences of the African
American community through the lens of individuals from the community as participants. I hope
to bring forward policy options that supports health equity thus resulting in improved health
outcomes with the consideration of lived perspectives of the African American community
gleaned from the intended interviews. The intended strategic objectives of this research include
promoting efficient health policy changes that will improve health outcomes for POC, especially
as it relates to African Americans thus effectively improving the relationship between the African
American community and health care institutions in the United States. Another objective is to
influence the promotion of an improved health care delivery prototype from a socio-political lens
that benefits marginalized groups and eventually helps to eliminates help inequities in the long
run.
Research Question
The research question for this qualitative study was as follows: What do African
Americans think about the impact of CIBHC on their own health outcomes and health care
delivery for POC?

9
Conceptual Framework
Three frameworks grounded this study: the institutional analysis and development
framework (IAD), the health equity framework (HEF), and the intersectionality-based policy
analysis framework (IBPA). The IAD framework allows for analyzing policy interventions and
how institutions develop, the critical elements involved in decisionmaking within the policy-
making process, and how these are influenced by exogenous variables (Ostrom, 2011).
Sanderson et al. (2020) extended Ostrom’s IBPA to include resource appropriation to capture
resource utilization in production chains as it relates to health service delivery in the case where
fund extraction is not the end, but the value of resources depends on how they are utilized.
The HEF is a model that describes the ways that health and education outcomes are
influenced by complex interactions between people and their environments as it relates to health
equity from a multilevel perspective (ETR, n.d.). The HEF encourages thinking outside of the
traditional norms that focuses on individual behaviors and choices and focuses. Rather HEF
centers on outcomes at a population level that targets access to resources and opportunities and
the personal agency that influence health equity.
The IBPA framework, which is built on the guiding principles of intersectionality, aims to
enhance the decision-making capacity of stakeholders, most especially in health and health
policy sectors, as it relates to equity-based improvements and social justice within complex and
diverse populations (Hankivsky, 2012). McBride et al., 2022; Cook et al., 2017; Mac-Seing et al.,
2020 extended Hankivsky’s IBPA framework for use to address health disparities as it relates to
health policies in various facets. In Chapter 2, I further discuss the IAD, HEF, and IBPA and their
application to the present study

10
The lack of the administration of health care policy on inequitable health care delivery in
the United States that has negatively impacted African Americans with cooccurring health
conditions, continues to severely contribute to poor health outcomes and further contributes to
health inequities. It further narrates the need to address SDoH that is culture specific to
improving health outcomes for African Americans. Using Ostrom’s IAD (2011) as the primary
framework that will ground this study, the problems will be analyzed to explore practical and
efficient interventions in collaboration with the federal government and community-based
organizations (CBOs) such as FQHCs, nonprofit organizations, and so forth. These are settings
where care can be administered to patients especially since it is part of the goals of the CDC’s
Healthy People 2030 directive as it pertains to one of the SDoH domains: health care access and
quality (DHHS, Office of Disease Prevention and Health Promotion, 2022).
As the actors or in this case, the federal government and the CBOs collaborate while
assuming their specific positions in the action arena to understand the scope, the
"what" and the "why," and explore interventions around the phenomenon of CIBHC care using
Hankivsky IBPA framework to guide equity-specific analysis in the development of
intersectionality based ‘potential outcomes’ for which cost and benefits can be weighed for which
outcomes can be determined that will best serve African American patients.
In the study of outcomes using ETR’s HEF to analyze the buy-in of African American
patients into the model of CIBHC from a health equity lens concerning the interaction between
patients in the community and their providers at the CBOs where they receive care. Within the
aggregation rule, using the evaluation of those variables to examine against the community,
biopsychosocial conditions, and the remaining rules in terms of influence on actors for then to

11
form possible policy suggestions to address health inequities to improve health outcomes in the
long term. In Chapter 2, I will further discuss the theoretical models.
The exploratory qualitative approach often grounds qualitative research inquiries based
on assumptions derived from people's perceptions. Interviewee responses are influenced by
individuals’ beliefs and values internalized through perceived susceptibility, perceived needs,
severity, barriers, knowledge, experiences, sensitivities, and cognitive abilities (Janz & Becker,
1984). The exploratory qualitative approach will allow for increased exploration of the sampling
area (the FQHC) and participants (African American patients with co-occurring conditions) using
semistructured, openended, descriptive interviews to interpret participant experiences to collect
data and compare individual responses (Rudestam & Newton, 2015). This approach will provide
further insight into patients’ perspectives regarding their experiences with the providers in hopes
of taking that direct contact to influence possible policy regarding culturally integrated health
care.
Nature of the Study
This study will involve a qualitative research design. A qualitative design allows for
flexibility in the setting, in this instance an FQHC in Bedstuy, Brooklyn, NY, and the participants
who are African American patients receiving health services. This design was chosen because
very little information is known as it relates to FQHC-based populations' experiences and health
care access and quality needs as it relates to this research area. The data gained from participants
relate to the lived experiences of African American patients and their experiences with their
providers who incorporate cultural care that take into consideration the access and quality
concerns that that influences low health outcomes.

12
Data for this study will be acquired via interviews, audio recordings, and patient records
(PHI) from the FQHC upon permission. Exploratory approaches are designed to pursue the
understanding of a phenomenon as it relates the value of a problem and offering an answer to the
presented research question(s) (Yin, 1994) as would be the case in this study. The approach will
also help to explain the problem through the lens of the participants in the study. In Chapter 3, I
will further expound on the study procedures.
Data will be obtained from participants about their perceived experiences with their
providers when receiving care using semistructured, open-ended, descriptive interviews. This
approach allowed for sufficient time to be spent with participants to ensure the accuracy of the
data. Due to the population the study is concerned with, purposeful sampling which will be used
to select participants who are residents of the five boroughs of New York City (NYC), between
the ages of 18-75, have a diagnosis of both a chronic and behavioral health disorder, and are
African American. The analysis may help researchers, policymakers, and health administrators,
identify themes that can help facilitate change for the betterment of African Americans and their
relationships with health care institutions.
Definitions
Community-Based Organizations (CBOs): “a public or private nonprofit organization of
demonstrated effectiveness that (A) is representative of a community or significant segments of a
community; and (B) provides educational or related services to individuals in the
community.”(Community Based Organizations, 2011, Sect §7801.6)
Collaborative Care model (CoCM): An integrated care model developed by University of
Washington researchers and practitioners to treat patients with behavioral health conditions. It

13
utilizes a measurement-based, treatment-targeted approach through coordinated efforts between
primary care providers (PCPs) and behavioral health professionals. Evidence-based treatments
are delivered through a combination of medication, psychotherapy, and continuous assessments
tailored to the patient's needs (Advancing Integrated Mental Health Solutions Center [AIMS]
Center, n.d.).
Culturally Integrated Behavioral Health Care (CIBHC): This model offers highquality,
coordinated care led by primary care and behavioral health teams working collaboratively with
patients and families. It is designed to address mental health, substance use, health behaviors
(including management of chronic illnesses), life stressors, and patterns of ineffective health care
utilization. Care delivery emphasizes cultural humility (Mosher et al., 2017), respects patient
diversity in both the physical environment and care practices, and fosters a partnership dynamic
between patients and providers based on empowerment and patient-centeredness (Holden et al.,
2012).
Federally Qualified Health Centers (FQHCs): “Public health centers that serve at-risk
and underserved populations, offering comprehensive care regardless of the patient's ability to
pay. They are eligible for Section 330 grants under the Public Health Service Act” (Health
Resources and Services Administration, 2022).
Primary Care Association: “These are nonprofit organizations at the state or regional
level that provide training and technical assistance (T/TA) to safety-net providers. Their support,
tailored to regional and statewide needs, helps health centers enhance clinical, programmatic, and
financial performance. PCAs [primary care organizations] also assist in strategic planning for

14
health center expansion and staff recruitment/retention efforts” (Health Resources and Services
Administration, 2022)
Serious Mental Illness: “A mental, behavioral, or emotional disorder (or combination of
disorders) that results in significant functional impairment, substantially interfering with or
limiting one or more major life activities.” (NIMH, 2020).
Assumptions
The assumptions of any study are determined by the research approach and the
philosophical foundations (Ravitch & Carl, 2021). Qualitative inquiry positions that the
researcher designates the description of a phenomenon to which the meaning is then elaborated
(Patton, 2015). When distinguished from other limitations in qualitative studies, qualitative
assumptions should be understood that the researcher does not control assumptions. It should
also be understood that the what questions concerning the research are fundamental to
establishing value. Assumptions typically have to be associated with trustworthiness in terms of
credibility, transferability, and conformability.
The following were the underlying assumptions for the current study based on relevant
literature. I assume that participants will be forthcoming about their experiences as well as be as
truthful as possible about the telling of those experiences since this is such a personal matter. I
assume that a qualitative approach is the best for this study because it will likely produce
meaningfully societal and culturally constructed conditions and values that lend to people’s
perspectives (Rudestam & Newton, 2015). Considering African Americans are one of the most
affected groups that have been plagued by health disparities for centuries in American history,
they bring a unique perspective as it relates to health care. In fact, it’s because of that unique

15
perspective that I believe can influence this study, it’s outcome and eventual policy goals. It
should also be noted, that despite the advancements in health reform the last few years, the fact
remains that marginalized groups still remain at risk for health inequality. This is due to
determinants such as access to care, health security, difference in quality, unmet health needs and
so forth (Riesling et al, 2022). As it relates to integrated behavioral health care, using the CoCM
has the potential to influence better health outcomes while improving quality (Deis, 2022),
especially as it relates to African Americans and the assumption of supported health policies that
will also help to increase those odds.
Scope and Delimitations
Delimitation of a study concerns narrowing the scope while establishing parameters of
participant recruitment and research context (Bloomberg & Volpe, 2018). While the role of
FQHCs in health care delivery is known for underserved populations, the role of FQHCs in the
context of CIBHC delivery is to improve the health outcomes of African Americans. The
exploratory qualitative approach used in this study will capture the essence of participants'
experiences with their providers as it relates to the perspectives of health care quality and access
so that results will capture the SDoH that affects participants as it relates to their socioeconomic
influences. While the current study acknowledges the prevalence of health inequities among
other groups of color, the main focus is on African Americans because of their specific history
related to the intersectionality of bias and health care (Bailey et al., 2017; Adekson, 2021).
The participants in this study are well informed as well as selected because of their
specific understanding, knowledge, and readiness to discuss their personal experiences as African
Americans in relation to their personal experiences with health care providers. Since the setting is

16
an FQHC, providers are defined as PCPs, nurse practitioners, physician assistants, clinical
psychologists, and social workers (CMS, 2024). Participants are involved in face-to-face
interviews in which they respond to openended questions. The interview will be guided by an
interview guide which helps to ensure the accuracy of the questions being asked.
Limitations
In qualitative research, limitations are defined as shortcomings or drawbacks of a study
that can influence the outcome of a study (Ross & Zaidi, 2019). Based on this definition, one of
the limitations is the sample size, and considering the study is only covering the borough of
Brooklyn within NYC- given the limited time and resources to cover the stakeholders (
participants) given the prominence of this policy matter, the interview will be limited to patient
perspectives as it relates to their health care experience concerning the care, integrated behavioral
health care, culture as it relates to SDoH specific to the African Americans and health care
institutions. Another limitation of this study is the potential bias that might arise on the part of the
particular experiences African Americans have had in the United States. To mitigate any potential
bias in this regard, participants will be educated on the importance of how the contribution of
their personal experience in relation to health care can contribute to making a change in how
health disparities are addressed through a policy lens.
Another significant limitation is credibility and transferability. Credibility is established
by having particular procedures of the research protocol and the recording protocols (Walden
University, 2014). Transferability refers to assessing how the results of a study can be generalized
in different contexts (Nowell et al., 2017). Because the study is based on participants' experiences
in their own words, everything must be captured accurately, as participants will be aware that the

17
interview will be recorded to ensure correctability, and they will be informed of how the data will
be disposed of upon the conclusion of the study. Another limitation of this study will likely be
due to the fact this study will be at one FQHC, it limits the generalizability of the outcomes or
results. And also, because this study is a qualitative study it makes it a bit more difficult to
generalize the experiences of all participants who might receive integrated behavioral care
(Siantz et al., 2020).
Significance of the Study
This study is significant because it raises awareness of health care disparities as a
contributing factor low health outcome amongst African Americans, raises awareness for
culturally integrated health care, attaining health equity, especially for African Americans and
other minorities in the United States, requires appropriate policy design and implementation.
Before new policies can be created, existing ones changed, or pending ones adopted, there needs
to be an understanding as to how providers and recipients of services experience existing
policies. The results of the intended study may provide the literature information about the
perspectives of African Americans about the benefits of culturally integrated care that seek to
take into account and address social determinants specific to African Americans' approach to
care. The intended study hopes to provide information from unique experiences in health care
that will provide data that can have a sustainable impact in engaging in dialogue and action with
stakeholders/ change agents that can help facilitate change for the betterment of African
Americans and their relationships with health care institutions. Positive social change may
increase and sustain efficacious health care policy response that will not only set forth political
change but, most importantly, thereby reduce unnecessary loss of life amongst African

18
Americans for diseases and disorders that can be addressed and improving outcomes and the ability
to reach their full health potential without the fear of negative determinants that does not make that
a choice.
Significance to Practice
The outcomes of the study may contribute to health policymakers prioritizing policies
specific to CIBHC in the United States while encouraging federal health agencies such as CMS,
DHHS, CDC, and so forth to implement policies and interventions as well as collaborate with
CBOs and FQHCs to maximize improved health outcomes for all marginalized groups but more
specifically African Americans, thus improving the overall quality of life for individuals and
communities of African Americans in the United States. As it relates to health system delivery
and SDoH, the results of this study have the potential to improve health care quality and access
for African Americans. As a public good, an efficient and effective policy could help achieve the
overarching goal stressed in this study.
Significance to Theory
The outcomes of the study have the potential to contribute to academia, scholarships,
training and further understanding as it relates to health equity. As it relates to theory, the
outcomes of this study may have the potential to contribute towards all mentioned frameworks
for this study. As it relates to HEF, the outcomes of this study have the potential to further
promote health equity through the lens cultural perspectives and its importance to addressing root
causes of socioeconomic concerns that contribute to health inequality. While HEF addresses
systems of power such as health care systems, the results of this study has the potential to present
theoretical and policy insights towards minorities overcoming disparities that have contributed to

19
poor outcomes. Information learned will also provide more nuanced theoretical foundations for
policymakers and researchers. Pertaining to the remaining two frameworks, the outcomes of this
study present information that lends as a foundation to the policy process through the various
institutions involved working together and effectively for the purpose of health equity. From the
health care systems, to the African American communities, to the policymakers and so forth
while considering the perspectives of those most affected by health disparities to provide better
access and quality that influences better outcomes for African
Americans.
Significance to Social Change
The findings of the study have the potential to make evidence-based decisions regarding
health policy that promotes the most significant benefit for the most people. The findings may
present an opportunity for communication and implementation between stakeholders to promote
the importance of culturally integrated (behavioral) health care that benefits all involved but,
most importantly, those most affected by chronic health conditions. The implications of this also
has the potential to influence new paradigms within health care policy as it relates to benefiting
marginalized groups in the long run that promotes better health outcomes. But most importantly,
the social change implications will positively affect health care equity and African American
health outcomes and overall quality of life.
Summary
In this chapter, I introduced health disparities and the significance of problems within the
health care system in the United States as a need to shrink the gap in research. As the identified
problem was the lack of policy regarding integrated care that took considered the social

20
detriments specific to marginalized groups- specifically African Americans- therefore the reason
for the continuance of low health outcomes thereby continuing the hand in health care disparities.
The purpose of this qualitative study was to explore and understand culturally appropriate
integrated care through the perspective of the African American experience in health care from a
public policy lens, particularly regarding culturally integrated (behavioral) health care. The study
focused on the consideration of SDoH and systemic policy disparities that play a role in the
approach to care for African American patients, the need to improve health outcomes, and the
need for effective policy that helps improve health outcomes through the integrated care
approach. In Chapter 1, I described the approach, the background, the research question, and the
significance of the study. In Chapter 2, I review and synthesize relevant literature that includes
the theoretical foundation, related concepts, and gaps in the literature, all while contextualizing
the study from a public policy lens. In Chapter 3, I explain the methodology used in the study.
Chapter 2: Literature Review
Introduction
Bias is rooted in the fabric of human history. However, more germane to this study is
racism, rooted in the history of the United States. This stained memoire has continued to affect
all aspects of everyday life in America, so much that it has become a detriment to the quality of
life for all citizens, particularly as it relates to African
Americans in the United States (Bleich et al., 2019). Examples of this include the Antebellum
period (1789 to 1861), which established the enslavement of Africans within the colonies as well
as a racial caste system based on the principle of inferiority. The principle, originally established
by John Locke, was later bolstered by Thomas Jefferson in the drafting of the Constitution as it

21
related to Blacks in the United States at the time. The same belief would be used in the creation
of Declaration of Independence despite the political revolution for freedom (Finkelman, 2012;
Roediger, 2020).
With the Reconstruction Era (1865 to1880), though slavery became formally abolished,
this period brought hope for African Americans such as the passage of the 14th and 15th
amendments – which granted full U.S. citizenship and extended the right to vote for Black men;
the Freedman’s Bureau which was authorized as a brief U.S. social service agency for refugees
and freedmen and their families (University of Maryland,
2022). But this swift period would prove to be short lived. Post-Reconstruction (18761965)
introduced institutional and legal racism against African Americans formally known as Black
Codes and Jim Crow laws. It is during this time, that systemic and discriminatory policies that
affected daily life for African Americans that promoted separate and unequal treatment- a
practice that also upheld by SCOTUS. As evidenced by racial terrorism that resulted in lynchings
initiated by the Ku Klux Klan, scare tactics so African Americans did not vote, redirection of
government resources intended for Black communities that were often given to White
communities, and massacres of thriving Black communities (Darity & Mullen, 2020). Some
examples of these tactics include: disenfranchisement policies such as poll taxes and literacy
tests before voting, waves of massacres committed on successful Black communities that often
resulted in loss of property and economic opportunity specifically between 1863 and the 1940s
(Hodge et al, 2021), and resources for housing or schools intended for the Black communities
would often be given to White communities.

22
Specifically, the period between World War II which began in 1939 and the Civil Rights
Era which would end around 1970 the principle of inferiority remained, but it existed in the
dimension of separate but equal. African Americans would face systematic, discriminatory, and
institutional racism during this time, such as inadequate facilities and accommodations, increased
violent murders of African Americans, and redlining practices (Darity & Mulling, 2020). From
the 1980s to the Present, African Americans have and continue to experience mass incarceration,
drug disparities, increased police brutality, and a new wave of White supremacy known as the
alt-right movement.
Regrettably, these recorded examples in history, as a consequence, correlate to why
African Americans suffer more from chronic disease combined with a behavioral health
diagnosis, thus resulting in mortality rates exponentially higher in comparison to other races
(Glenn et al., 2018). Unfortunately, it would take the United States nearly 225 years to implement
a policy that attempted to address inequalities that targeted underserved communities and
acknowledged the non-medical factors that influence health outcomes such as biological,
behavioral, sociocultural, economic, and ecological by brigading the gap between community-
based health and health care, that policy is known as the ACA (2010; Dawes, 2018). Even with
such a landmark passage, the ACA failed to promote the need for an integrated health care
system that considers SDoH.
Integrated health care has the opportunity to improve access to comprehensive care, and
the quality of care received, and overall could potentially reduce racial disparities in health care
(Lewis & Myhra, 2018; O’Loughlin et al., 2019). While there has been advocacy by federal
agencies, CBOs, and various stakeholders for integrated care, therein is a lack of health care

23
policy as it relates to the consideration for intersecting SDoH and systematic policy disparities
that play a role in the approach to African American patient’s care, thus the need for a culturally
appropriate integrated care approach to improve health outcomes. This qualitative study aims to
understand culturally appropriate integrated care from a public policy lens through the
perspective of the African American experience in health care.
In Chapter 2, I will discuss the following: the relevant conceptual and research
background underpinning the study, the literature search strategy, and the parameters of the
search, as well as the supporting theories that support the primary conceptual approach of the
study. Next, the literature on SDoH and its history, health disparities, policy measures concerning
SDoH, integrated care; and the insufficient research that has been published on the lack of policy
implementation about culturally integrated care that recognizes and addresses specific SDoH that
influence low health outcomes for African Americans. The chapter concludes with policy
attempts by the United States government to address health disparities, the literature gap, and a
chapter summary.
Literature Search Strategy
The literature review reflects the search and synthesis of studies on health policy, SDoH,
health disparities, racism, and integrated care. The intended goal of this literature search was to
identify relevant and recent literature as it relates to the topic. This literature review also includes
findings from seminal works and more recent literature related to the theories that underpin the
present study, as well as validating the study’s ability to contribute to existing knowledge
potentially. As it relates to the conceptual framework that underpins the current study, Ostrom’s
(1982) IAD framework was the main theory that grounded the study. This was complemented by

24
ETR's HEF and Hankivsky’s IBPA framework. I searched related content by using the following
search keywords: health services disparities, health systems, governance, common pool
resources, collective actions, policy analysis, intersectionality, reflexivity, and health equity.
To ensure the quality of the literature, peer-reviewed journaled articles (with abstracts),
government-published publications, books, online websites, and databases; published between
2018- 2022; with relevance to the subject matter; evidence of quality scientific standard in
research; and expanded geographical location outside of the United States. The literature search
conducted used multidisciplinary databases: EBSCO Host,
ProQuest Central, ProQuest Dissertation Publishing, CINAHL & Medline Combined, Political
Science Complete, Google Scholar, Congress.gov, and Govinfo.org. The key terms used to search
included different variations and mergers of terms: integrated care, African American or black or
POC, SDoH or social determinants of health; racism; health policy, inequality, policy, outcomes,
culturally integrated, healthcare disparities, health inequity, health status disparities, culture;
primary care; FQHCs; behavioral health care; integrated care; systemic disparities; health
Inequities; collective actions; health Commons; and health systems.
Conceptual Framework
As it relates to the inequality of African Americans and health care in the United States,
the issue is fundamentally based on structural racism. It works through laws and policies that
allocate resources in ways that marginalize and devalue particular racial or ethnic groups, often
creating unequal access to quality health care (Yearby, 2020). A practice that shaped early health
policy, or lack thereof, contributed to African Americans' poor health outcomes over time.
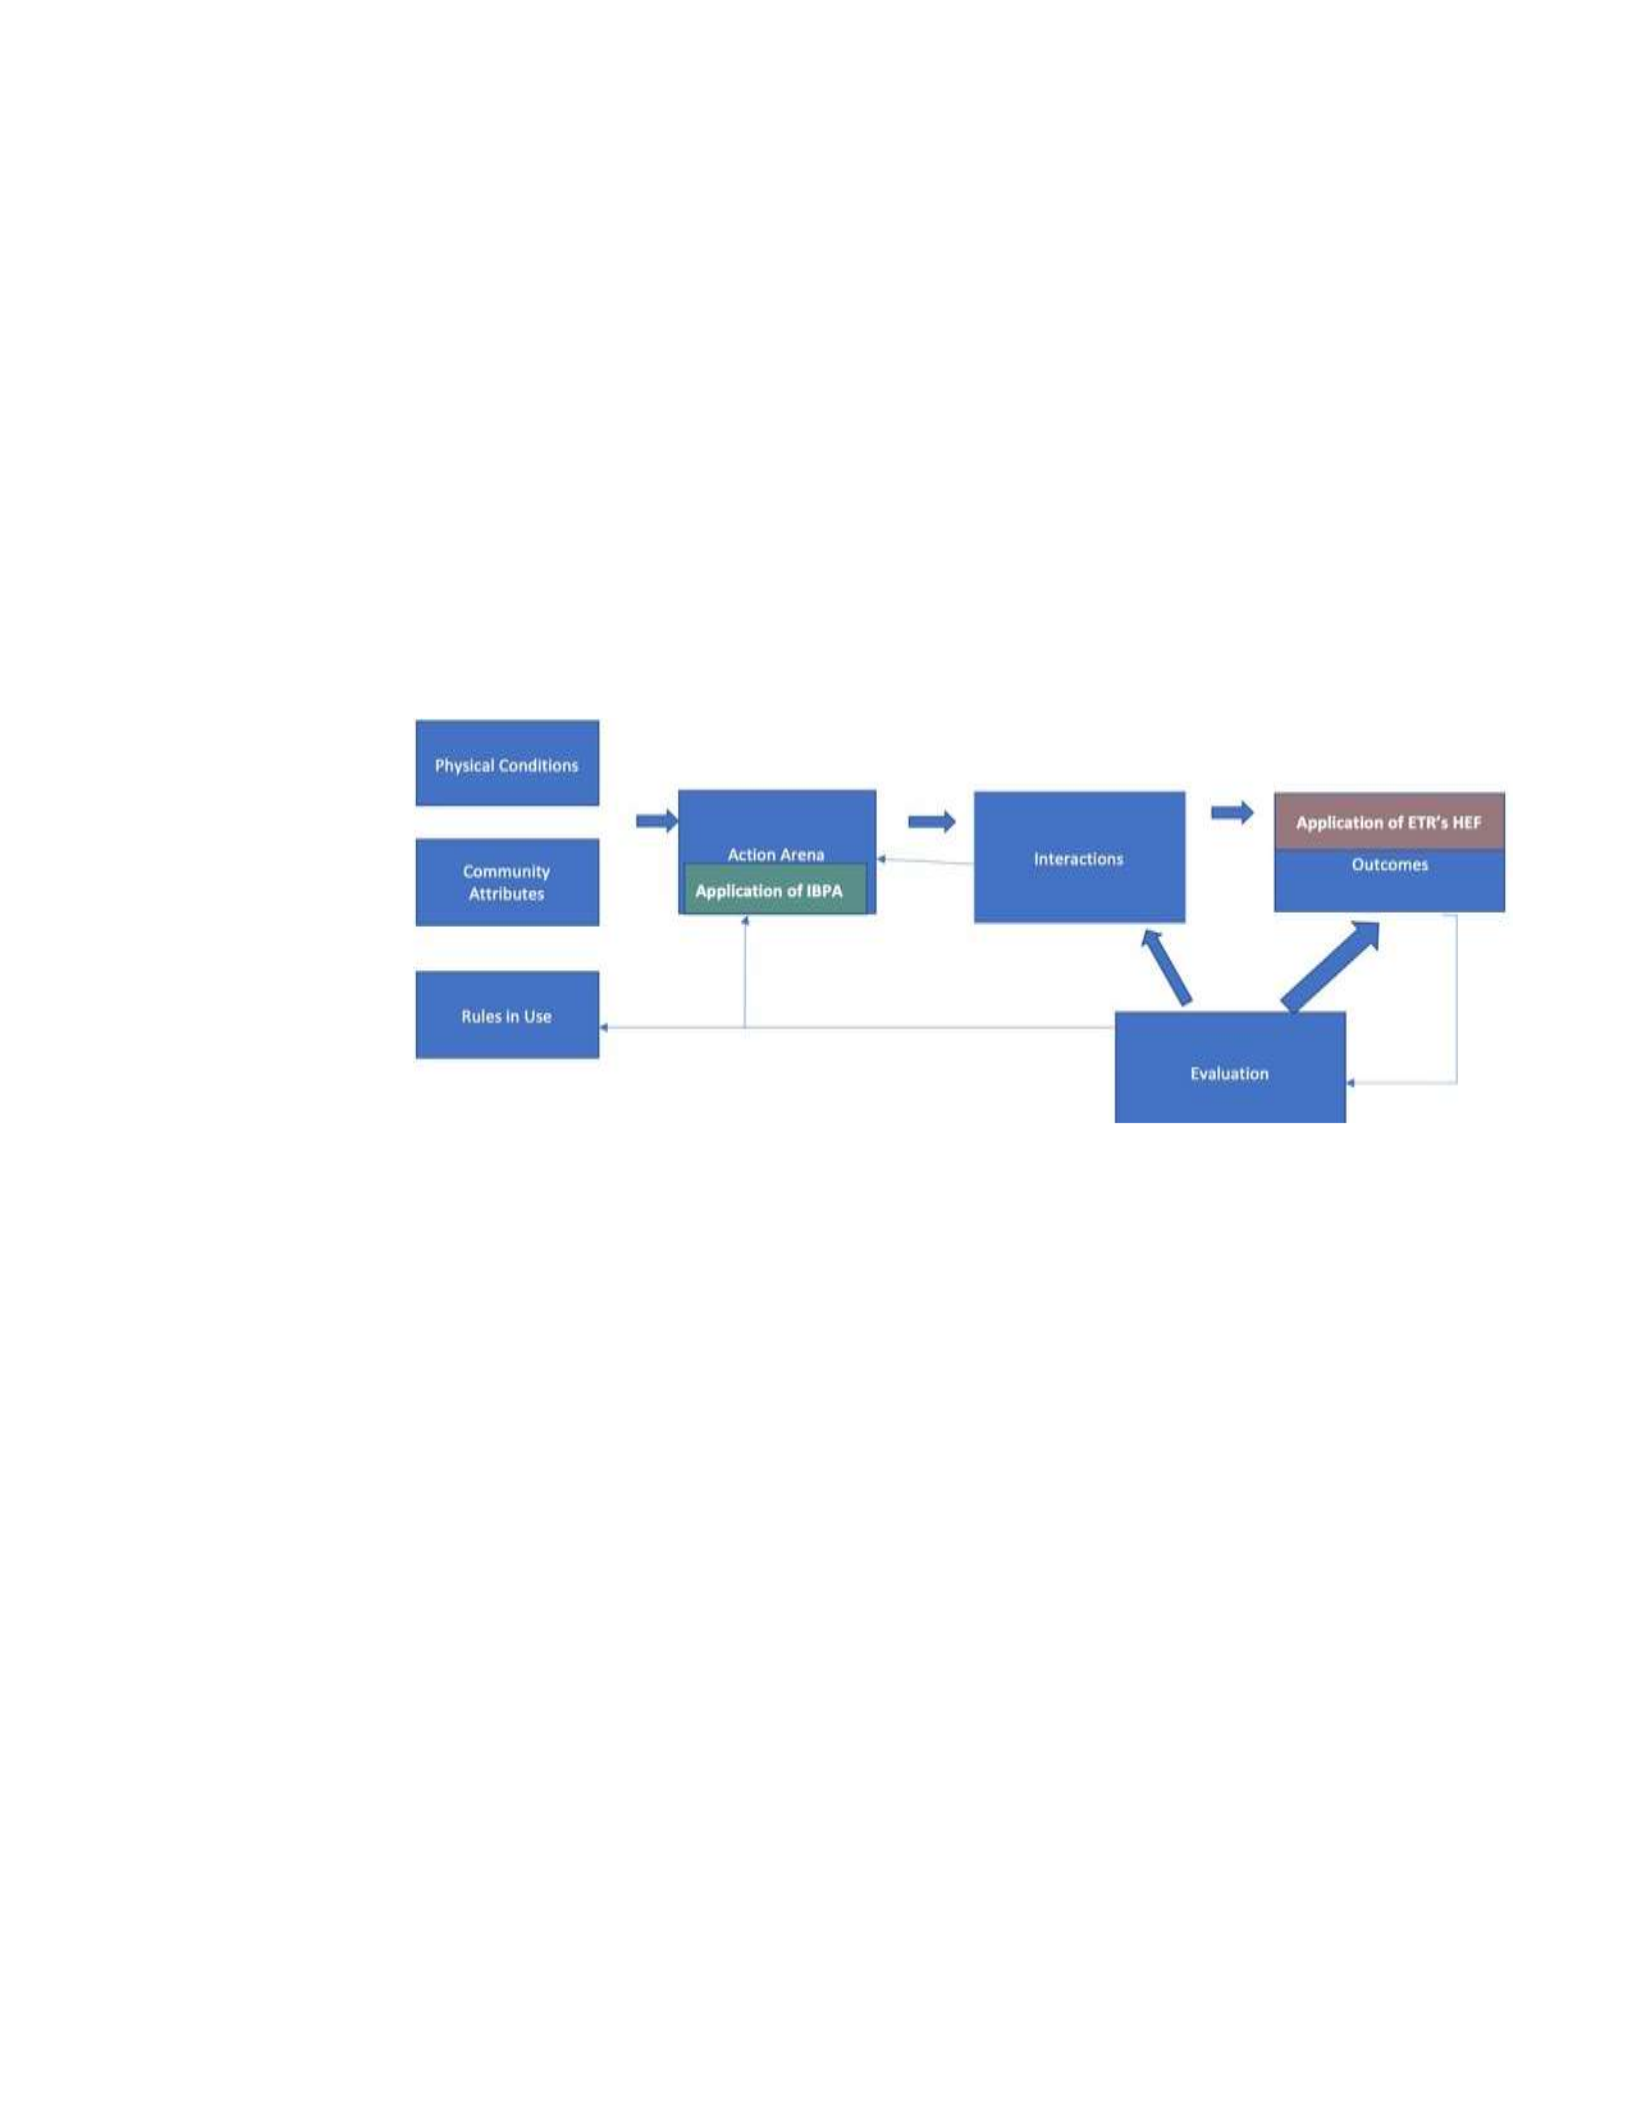
Against this backdrop, the conceptual framework that will ground this study is the IAD
25
framework as the main theory to understand health disparities and to be complemented by the
HEF and the IBPA framework to interpret the role of culturally integrated health care as it relates
to better health outcomes for African Americans from a policy lens. Figure 1 shows how the
integration of the frameworks for the purposes of this study.
Figure 1
Integrated Conceptual Framework
Note. The figure shows the integration of the institutional analysis and developmental, health
equity, and intersectionality-based policy analysis frameworks. IBFA = intersectionality-based
policy analysis; HEF = health equity framework.
Institutional Analysis and Developmental Framework
Ostrom postulated the IAD framework, but over time the framework has evolved through
the collective product of continued engagement of scholars who have participated in Ostrom’s
workshop (Ostrom & Polski, 1999; Ostrom, 2011; McGinnis, 2020). Initially, the framework was
intended to serve as a tool for simply analyzing institutions, but over time the context has
changed to include various institutional types that include health care. However, to understand

26
the true essence of the concept, one must understand the importance of frameworks concerning
the study of policy, institutions, and so forth, as is the case in this undertaking. In theoretical
analysis, frameworks are frequently employed to identify key elements and the general
relationships between them, which are necessary for conducting institutional analysis and
organizing both diagnostic and prescriptive inquiries. (Ostrom, 2011). How the variables and
elements interact with one another is examined. Thus, the elements in a framework help generate
needed questions (McGinnis, 2020). As is the case, a broad set of variables is then produced to
analyze institutional arrangements.
Scholars reasoned that institutional analysis is grounded in the following:
methodological individualism, bounded rationality, governance, and polycentricity (McGinnis,
2011; 2020). Methodological individualism posits that social, political, and economic
institutions are most effectively understood by recognizing that they are shaped by individuals
who act either independently or in coordination with others (McGinnis, 2011; 2020). “Bounded
rationality refers to the concept that individuals pursue their objectives while operating under
limitations in their cognitive abilities, available information, and the subtle effects of cultural
predispositions and beliefs “(McGinnis, 2011; 2020), which applies the similar concept of the
originator, Herbert Simon (1982) and likely would have agreed with the evolved manner in
which it is utilized here. Governance is the process of developing, enforcing, interpreting, and
adjusting rules, norms, and strategies within a particular area of policy (McGinnis, 2011; 2020).
Polycentricity describes a governance system where multiple authorities across various
jurisdictions interact to establish the conditions that define the actions permitted for both
authorities and citizens, while setting limits to serve the public good (McGinnis, 2011; 2020).But
27
as it relates to politically fragmented environments there often requires coordination modalities
between those who determine conditions for the purpose of decision making (Brethaut & Turley,
2020).
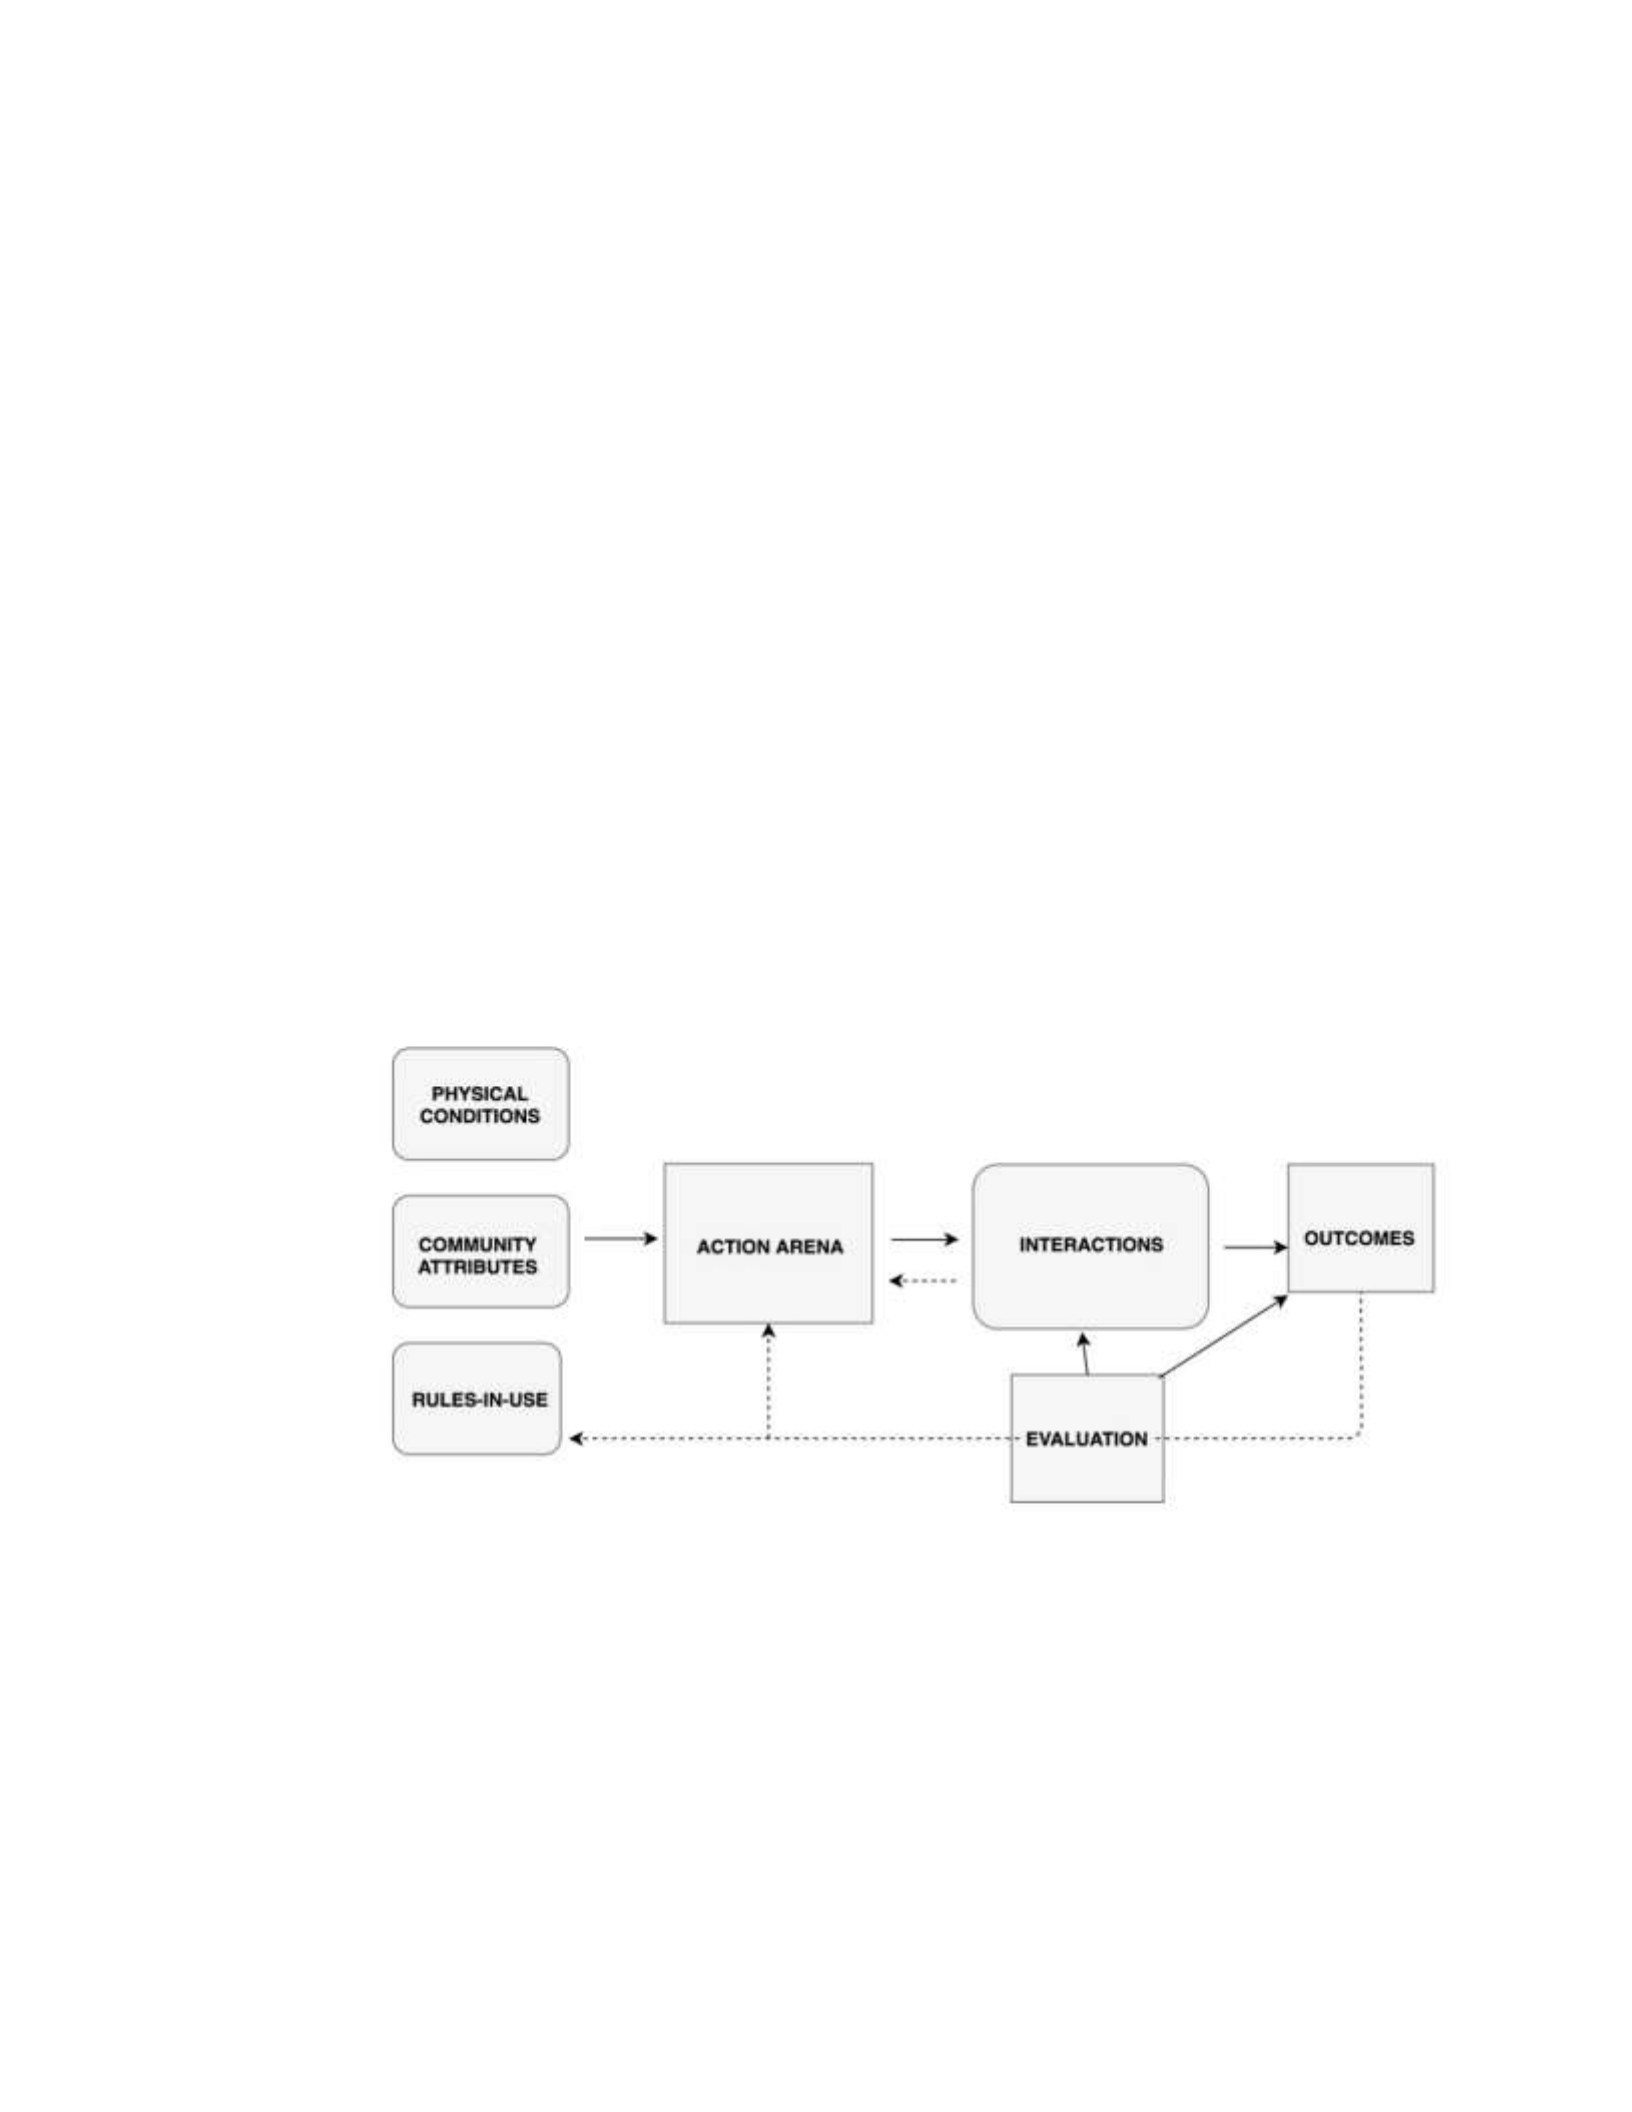
The IAD framework initially focused the analysis on the relationship among
institutions, cultural attributes, biopsychosocial conditions, human behavior, and action
(Ostrom, 2005; 2009). However, scholars have continually transformed the framework into
what Ostrom and other scholars accept as a multilevel conceptual map with interconnected
hierarchal parts of governance systems in a social system (see Figure 2).
Figure 2
Institutional Analysis and Development Framework
Note. From Understanding Institutional Diversity (p. 33), by E. Ostrom, 2009, Princeton
University Press. Copyright 2005 by Princeton University Press.
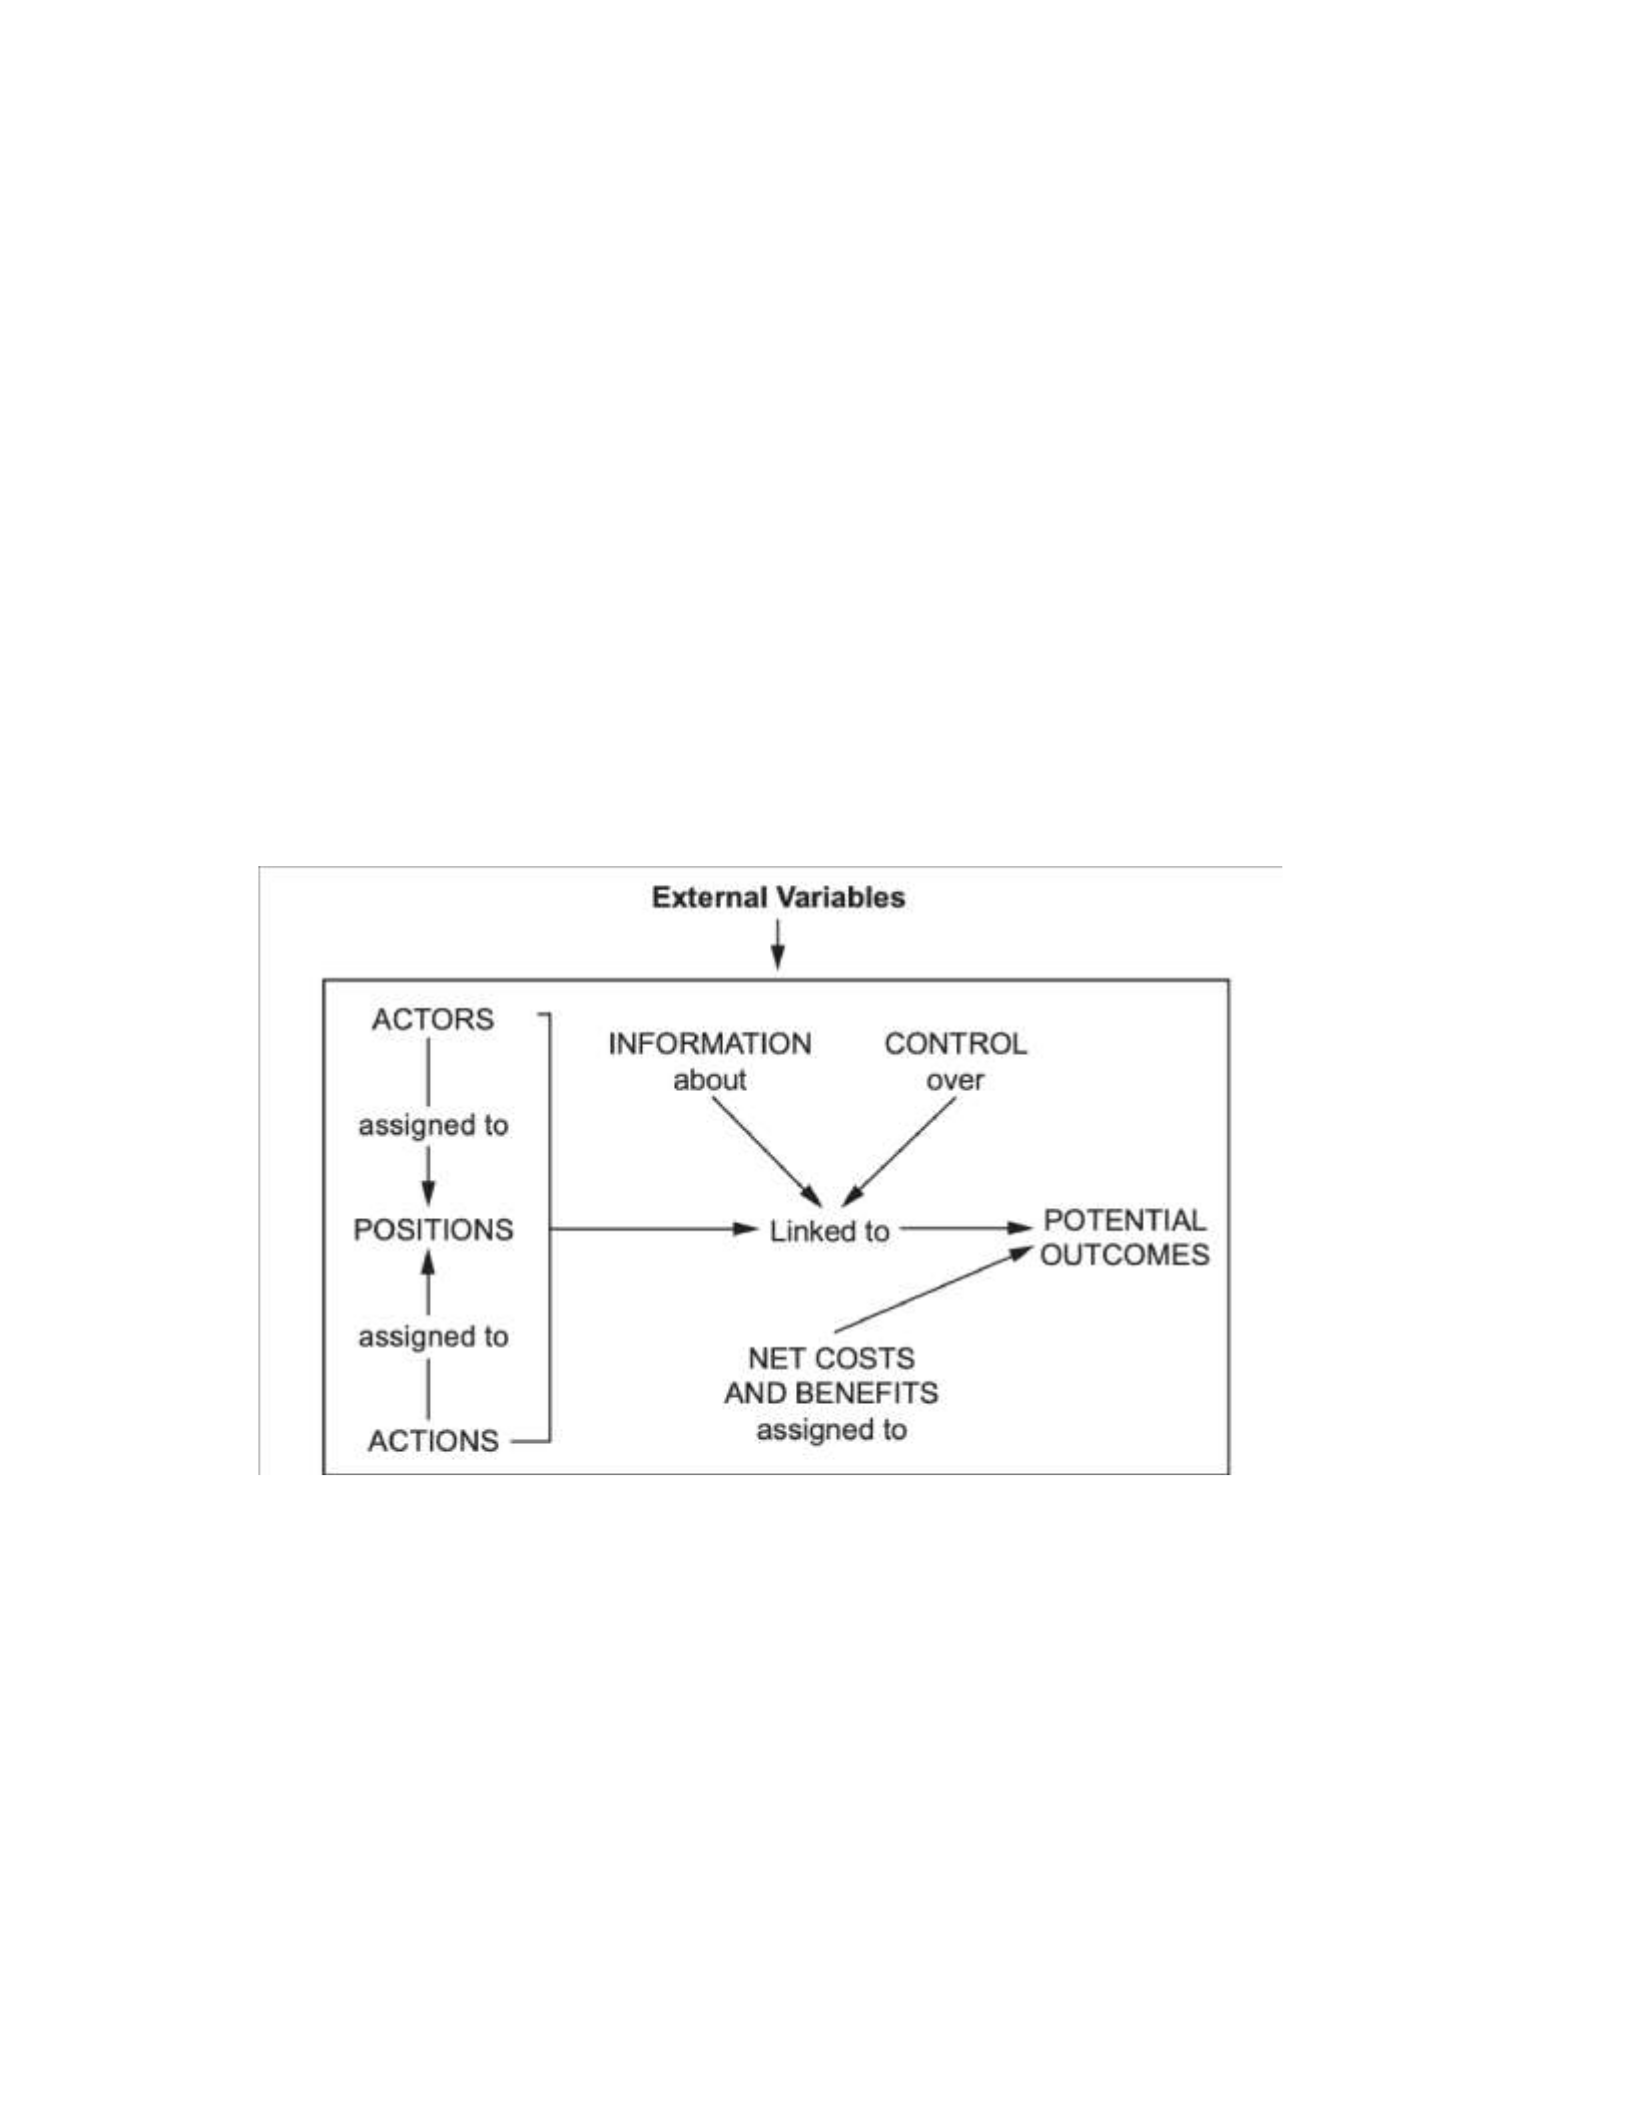
Figure 3 depicts the action arena, which is the IAD's central component. Within the
action arena, the action situation serves as the space where actors make operational,
28
collective, or constitutional decisions (McGinnis, 2020; Ostrom, 2005), leading to patterns
of interaction and outcomes. These outcomes are then evaluated (Ostrom, 2011), with
feedback loops and adaptive learning incorporated into the process (McGinnis, 2020).The
various types of individuals and organizations that typically make up the action arena are
tasked with weighing out the costs and benefits associated with actions and outcomes,
which also influence decisions (Heikkila & Andersson, 2021).
Figure 3
Internal Structure of an Action Situation
Note. From Understanding Institutional Diversity (p. 33), by E. Ostrom, 2009, Princeton
University Press. Copyright 2005 by Princeton University Press.
The process of analyzing an action situation within the action arena is as follows

29
(Ostrom, 2005): As a core component of the framework, participants who might be acting on their
own or as agents of an organization- would often observe information, select actions, engage in
patterns of interactions in which cost benefits analysis is performed based on the actions and the
potential outcomes and it’s from those interactions that they are able to realize the outcomes of
their interactions.
The analysis of institutions within the IAD framework is concerned with rules, more
particularly the who, what, and how in regard to participants involved, costs, associated risk, if
any, and the process of the establishment of newer rules (Lazo, 2019). Rules specify the values of
working compatibility with the biopsychosocial setting and community attributes. Rule typology
includes position- which determines the types and roles of decisions makers; boundaries- which
determine the entry, succession, and entry of actors; aggregation- which determines the collective
agreements; information - which determines information access; payoff- which identifies rewards
and sanctions and scope- which determines outcome variables (Heikkila & Anderson, 2018).
Upon evaluation of the action arena, the variables are also evaluated. Only then are the three
variables- the community, biopsychosocial condition, and rules -examined regarding their
influence on interactions with actors (Ostrom, 2005, McGinnis, 2020). Once these factors are
linked to action arenas, outcomes are formed.
Application of IAD Framework
The IAD framework has been applied in various contexts in examining, for example,
large-scale-ecosystems (Heikkila & Gerlak, 2018), fisheries (D. H. Cole et al., 2019), polycentric
(Neguse et al., 2019; Grossman, 2019), and so forth. However, concerning health disparities and

30
health policy, few contemporary studies used the IAD framework to conduct research in the
realm of health policy (Bae & Hysaung, 2018;
Lazo, 2019; Sanderson et al., 2020). For instance, consistent with the principles of the IAD
framework, the findings align with the framework's emphasis on collective action and resource
utilization. Sanderson et al. (2020), through case studies and interviews involving 22
participants—including providers, commissioners, local authorities, community providers, and
directors—along with three case studies from the English NHS over a year, discovered that while
there was reluctance to use Sustainability and Transformation Plans (STPs) to establish formal
rules for resource allocation, local actors engaged in collaborative decision-making to determine
how resources should be best utilized to improve health service delivery. This underscores the
importance of optimizing resources in line with collective approaches. Moreover, although state
involvement was perceived by some as coercive, it fulfilled a necessary role in ensuring
accountability, which is consistent with governance principles in the IAD framework. The study
also suggests that Ostrom's notion of resource "appropriation" should be broadened to capture the
complexities of resource utilization in health service delivery, where the value lies not in the
extraction of resources but in how they are applied, further aligning with the IAD framework’s
focus on resource efficiency in complex systems.
In a study that aligns with the principles of the IAD framework and serves as a foundation
for this research, Liu et al. (2021) sought to evaluate the quality of health care services provided
by community health centers (CHCs) from both the patient (demandside) and provider (supply-
side) perspectives. Based on interviews with 1,568 patients in Bay Area of China over a 3-month
period, the study revealed that service quality could be improved by enhancing institutional

31
health services in line with NCQA standards for patient-centered medical homes and by using
Primary Care Assessment Tool scales to assess patient experience (Liu et al., 2021). Consistent
with the IAD framework, the research also showed that CHCs operating at the meso-level have a
substantial impact on patient experiences at the micro-level (Liu et al., 2021). Therefore, to create
widespread change, efforts must start at the meso level.
In relation to public policy and the IAD framework, Brisboe et al. (2018) explored
collaborative governance as a means to address challenges associated with common pool
resources. The study integrated power theory into the IAD framework to examine forms of power
that are not typically captured by the IAD's focus on action situations, particularly through
Canadian collaborative processes involving energy interests (Brisboe et al., 2018). By assessing
the capacity to meet social and environmental goals, the study uncovered hidden power dynamics
related to inaction and non-decisions. It revealed that while collaboration led to progressive
outcomes, these were limited by the actors involved, selective rule enforcement, and a neoliberal
context that favored resource extraction (Brisboe et al., 2018). The findings highlighted that
powerful actors significantly influence decision-making processes and often benefit from
agenda-setting, which they help shape to align with their own interests (Brisboe et al., 2018).
However, by integrating power theory with the IAD framework, the study illuminated invisible
forms of inaction, non-decisions, and conditions that affect how the action arena is constructed,
populated, and executed (Brisboe et al., 2018). The interaction between these variables and the
actors in the action situation largely determines the ability of collaborative processes to achieve
desired outcomes (Brisboe et al., 2018).

32
Health Equity Framework
"Health equity" is a term that has been discussed more commonly in public health, but in
the last few years, it has lent itself to other fields, such as social sciences and public policy, as a
pressing priority. The health equity framework was postulated by Peterson, Charles, Yeung, and
Coyle as part of the behavioral nonprofit organization ETR; they developed this framework as a
science- and justice-based framework for promoting health equity (Peterson et al., 2021).
Nevertheless, it should be noted that this particular framework was developed based on existing
models that are also relevant to this study. To understand the essence of this framework, one must
recognize the fundamental essence of health equity and social determinants as it relates to public
health and social science.
When defining health equity, several key phrases frequently emerge, including:
“attainment or striving for the highest level of health, full health potential” or “optimal health;
fair and just opportunity,” “societal efforts or social conditions,” and the
“elimination of health disparities” (Office of the Assistant Secretary for Health [OASH],
2022). For the HEF, three functional definitions will be emphasized. First, Healthy People (2020)
defines health equity as achieving the highest level of health for all people, which requires
valuing everyone equally and addressing avoidable inequalities, historical and contemporary
injustices, and eliminating health and health care disparities through ongoing societal efforts.
Second, Braveman (2014) describes health equity as the principle guiding efforts to reduce and,
ultimately, eliminate disparities in health and its determinants, including the SDoH. Pursuing
health equity involves striving for the highest possible standard of health for all people, with
particular focus on those at greatest risk of poor health due to social conditions. Lastly, the CDC

33
defines health equity as providing everyone the opportunity to reach their full health potential
without being disadvantaged due to social position or other socially determined circumstances.
Commonly social determinants is associated with the following key phrases: “Conditions
in which people....”; “modifiable factors”; “fundamental; economic, environmental, and
historical forces or systems” (OASH, 2022). For HEF, the focus will be on two functional
definitions from Healthy People and WHO. Healthy People defines “the Social Determinants of
Health (SDoH) as the conditions in the environments where individuals are born, live, learn,
work, play, worship, and age, which impact a broad range of health outcomes, functioning,
quality of life, and risks” (Office of Disease
Prevention and Health Promotion, 2020). Similarly, the World Health Organization (WHO)
describes “SDoH as the conditions in which people are born, grow, work, live, and age, shaped
by a wide range of forces and systems that influence the circumstances of daily life” (WHO,
2019).
HEF is built based on previous models/frameworks, but the most notable or recognized
are the social-ecological model and Social Determinants of Health Framework (SDoHF). The
social-ecological model framework (see Figure 4) highlights the links between health and social
inequalities, particularly in areas such as education, income, employment, housing, and the
environment, which are critical social determinants influencing poor health outcomes. It
promotes strategies for disease prevention and health promotion by fostering action across these
key areas (Agency for Toxic Substances and Disease Registry, 2018). The social-ecological
model employs a multi-level framework to conceptualize health, emphasizing the complex
interplay between individuals, relationships, communities, and broader societal factors (OASH,

34
2022). Rather than focusing solely on individual behavior changes, the social-ecological model
prioritizes transforming physical and social environments to improve health outcomes (OASH,
2022).
Figure 4
Social-Ecological Model
Note. Adapted from “Principles of Community Engagement,” by Agency for Toxic
Substances & Diseases Substances, 2015, NIH Publication No. 11–7782
(https://www.atsdr.cdc.gov/communityengagement/index.html). In the public domain.
The SDoHF, developed as part of Healthy People 2020, is a place-based organizing model
that categorizes SDoH into five key areas: economic stability, education, social and community
context, health and health care, and neighborhood and the built environment (see Figure 5). Its
primary goals are to identify strategies for creating social and physical environments that foster
equitable opportunities for good health for all individuals, while specifically addressing the social
determinants that impact health outcomes (Healthy People, 2020).

35
Figure 5
Healthy People Social Determinants of Health Framework
Note. Adapted from Social Determinants of Health, by U.S. Department of Health and Human
Services, 2020 (https://www.healthypeople.gov/2020/topicsobjectives/topic/social-determinants-
of-health). In the public domain.
Earlier health equity frameworks have faced significant criticism for failing to effectively
reduce disparities, largely due to their neglect of the root causes of inequity (Hogan et al., 2018).
A further critique highlights the omission of the fundamental causes of racial health disparities
and the absence of a multi-layered approach (Yearby, 2020). Yearby emphasizes that both
government and public health officials need to acknowledge the connections between structural

36
discrimination, legal systems, and racial disparities (OASH, 2022). These critiques ultimately
contributed to the creation of ETR's HEF, which aims to address these gaps and challenges.
ETR’s HEF is one that builds on approaches from various fields such as public health,
education, and social science to illustrate how interactions between people influence health
outcomes are their environments, using that as a foundation to center on three concepts: equity at
the core of health outcomes; multiple, interacting spheres of influence; and historical and life-
course perspective (Peterson et al., 2021). Figure 6 illustrates the HEF.
Figure 6
ETR’s Health Equity Framework
Note. From “The Health Equity Framework: A Science- and Justice-Based Model for
Public Health Researchers and Practitioners,” by A. Peterson, V. Charles, D. Yeung, and

37
K. Coyle, 2021, Health Promotion Practice, 22(6), p. 743
(https://doi.org/10.1177/1524839920950730). CC BY-NC 4.0TF.
Equity at the Core of Health Outcomes
Health equity involves ensuring personal agency and fair access to resources and
opportunities necessary for achieving optimal physical, emotional, and social well-being
(Peterson et al., 2021). This concept emphasizes interventions designed to improve knowledge,
skills, and self-efficacy, with the aim of encouraging health-promoting behaviors for better
outcomes. However, the HEF recognizes that institutional and interpersonal biases limit access to
resources for certain communities, contributing to disparities and poor health outcomes.
Consequently, the HEF focuses on analyzing health outcomes at the population level rather than
the individual level, allowing stakeholders— such as researchers and government officials—to
address broader systemic factors that affect access to resources and opportunities (Peterson et al.,
2021). To achieve true health equity, practitioners must move beyond traditional approaches and
adopt strategies that engage multiple spheres of influence.
Multiple, Interacting Spheres of Influence
The HEF emphasizes the implicit and explicit interactions of multilevel influences on
health outcomes (Peterson et al., 2021). It identifies four key spheres of influence that shape
health outcomes and inform strategies to address inequities: systems of power, relationships and
networks, individual factors, and physiological pathways (Peterson et al., 2021). Systems of
power refer to the policies, processes, and practices that control the distribution and access to
resources and opportunities needed for health. These systems aim to address health disparities by

38
ensuring equitable access to these resources. Health equity policies are often enacted in political
and institutional spaces, which are key drivers of population health outcomes (Peterson et al.,
2021). Relationships and networks encompass the connections and support systems available to
individuals, which can act as protective influences against stigma, discrimination, and other
pressures that contribute to poor health. HEF underscores the significance of social relationships
in maintaining health (Peterson et al., 2021).
Individual factors relate to a person’s response to social, economic, and environmental
conditions through their attitudes, skills, and behaviors. HEF highlights the importance of these
individual factors and their interactions with broader spheres of influence. A person’s
characteristics, such as skills, attitudes, and behaviors, shape their experiences, including their
interactions with others and access to opportunities, which are often determined by systems of
power (Peterson et al., 2021). Lastly, physiological pathways refer to a person’s biological,
physical, cognitive, and psychological capacities. HEF acknowledges the critical role these
factors play in health outcomes, noting how the timing and intensity of environmental stressors
can affect physical, cognitive, or psychological functioning over the course of a lifetime. The
framework raises awareness of how interventions can strengthen and support these functions and
abilities, promoting resilience after exposure to stressors (Peterson et al., 2021).
Historical and Life-Course Perspective
In the context of the HEF, the life course is a key element. It involves a detailed
examination of the historical and developmental phases throughout an individual’s life, with an
emphasis on systemic and relational factors (Peterson et al., 2021). This approach takes into
account how cumulative experiences over a person’s lifespan and across generations contribute

39
to health inequities. To achieve equity, it is crucial to recognize and address how systems of
power have hindered access to essential resources and opportunities (Peterson et al., 2021).
Application of Health Equity Framework
As a recently developed approach, there is limited application of the HEF, but this study
will apply the framework in addressing the intended problem.
Intersectionality-Based Policy Analysis Framework
The IBPA framework was postulated initially by Hankivsky but has been refined over
time. IBPA aims to enhance the decision-making capacity of stakeholders, most especially in
health and health policy sectors, as it relates to equity-based improvements and social justice
within complex and diverse populations (Hankivsky, 2012). The goal of IBPA is to improve tools
for evaluation, such as health impact assessments- which often tackle health inequities when
making decisions at the policy and programming level
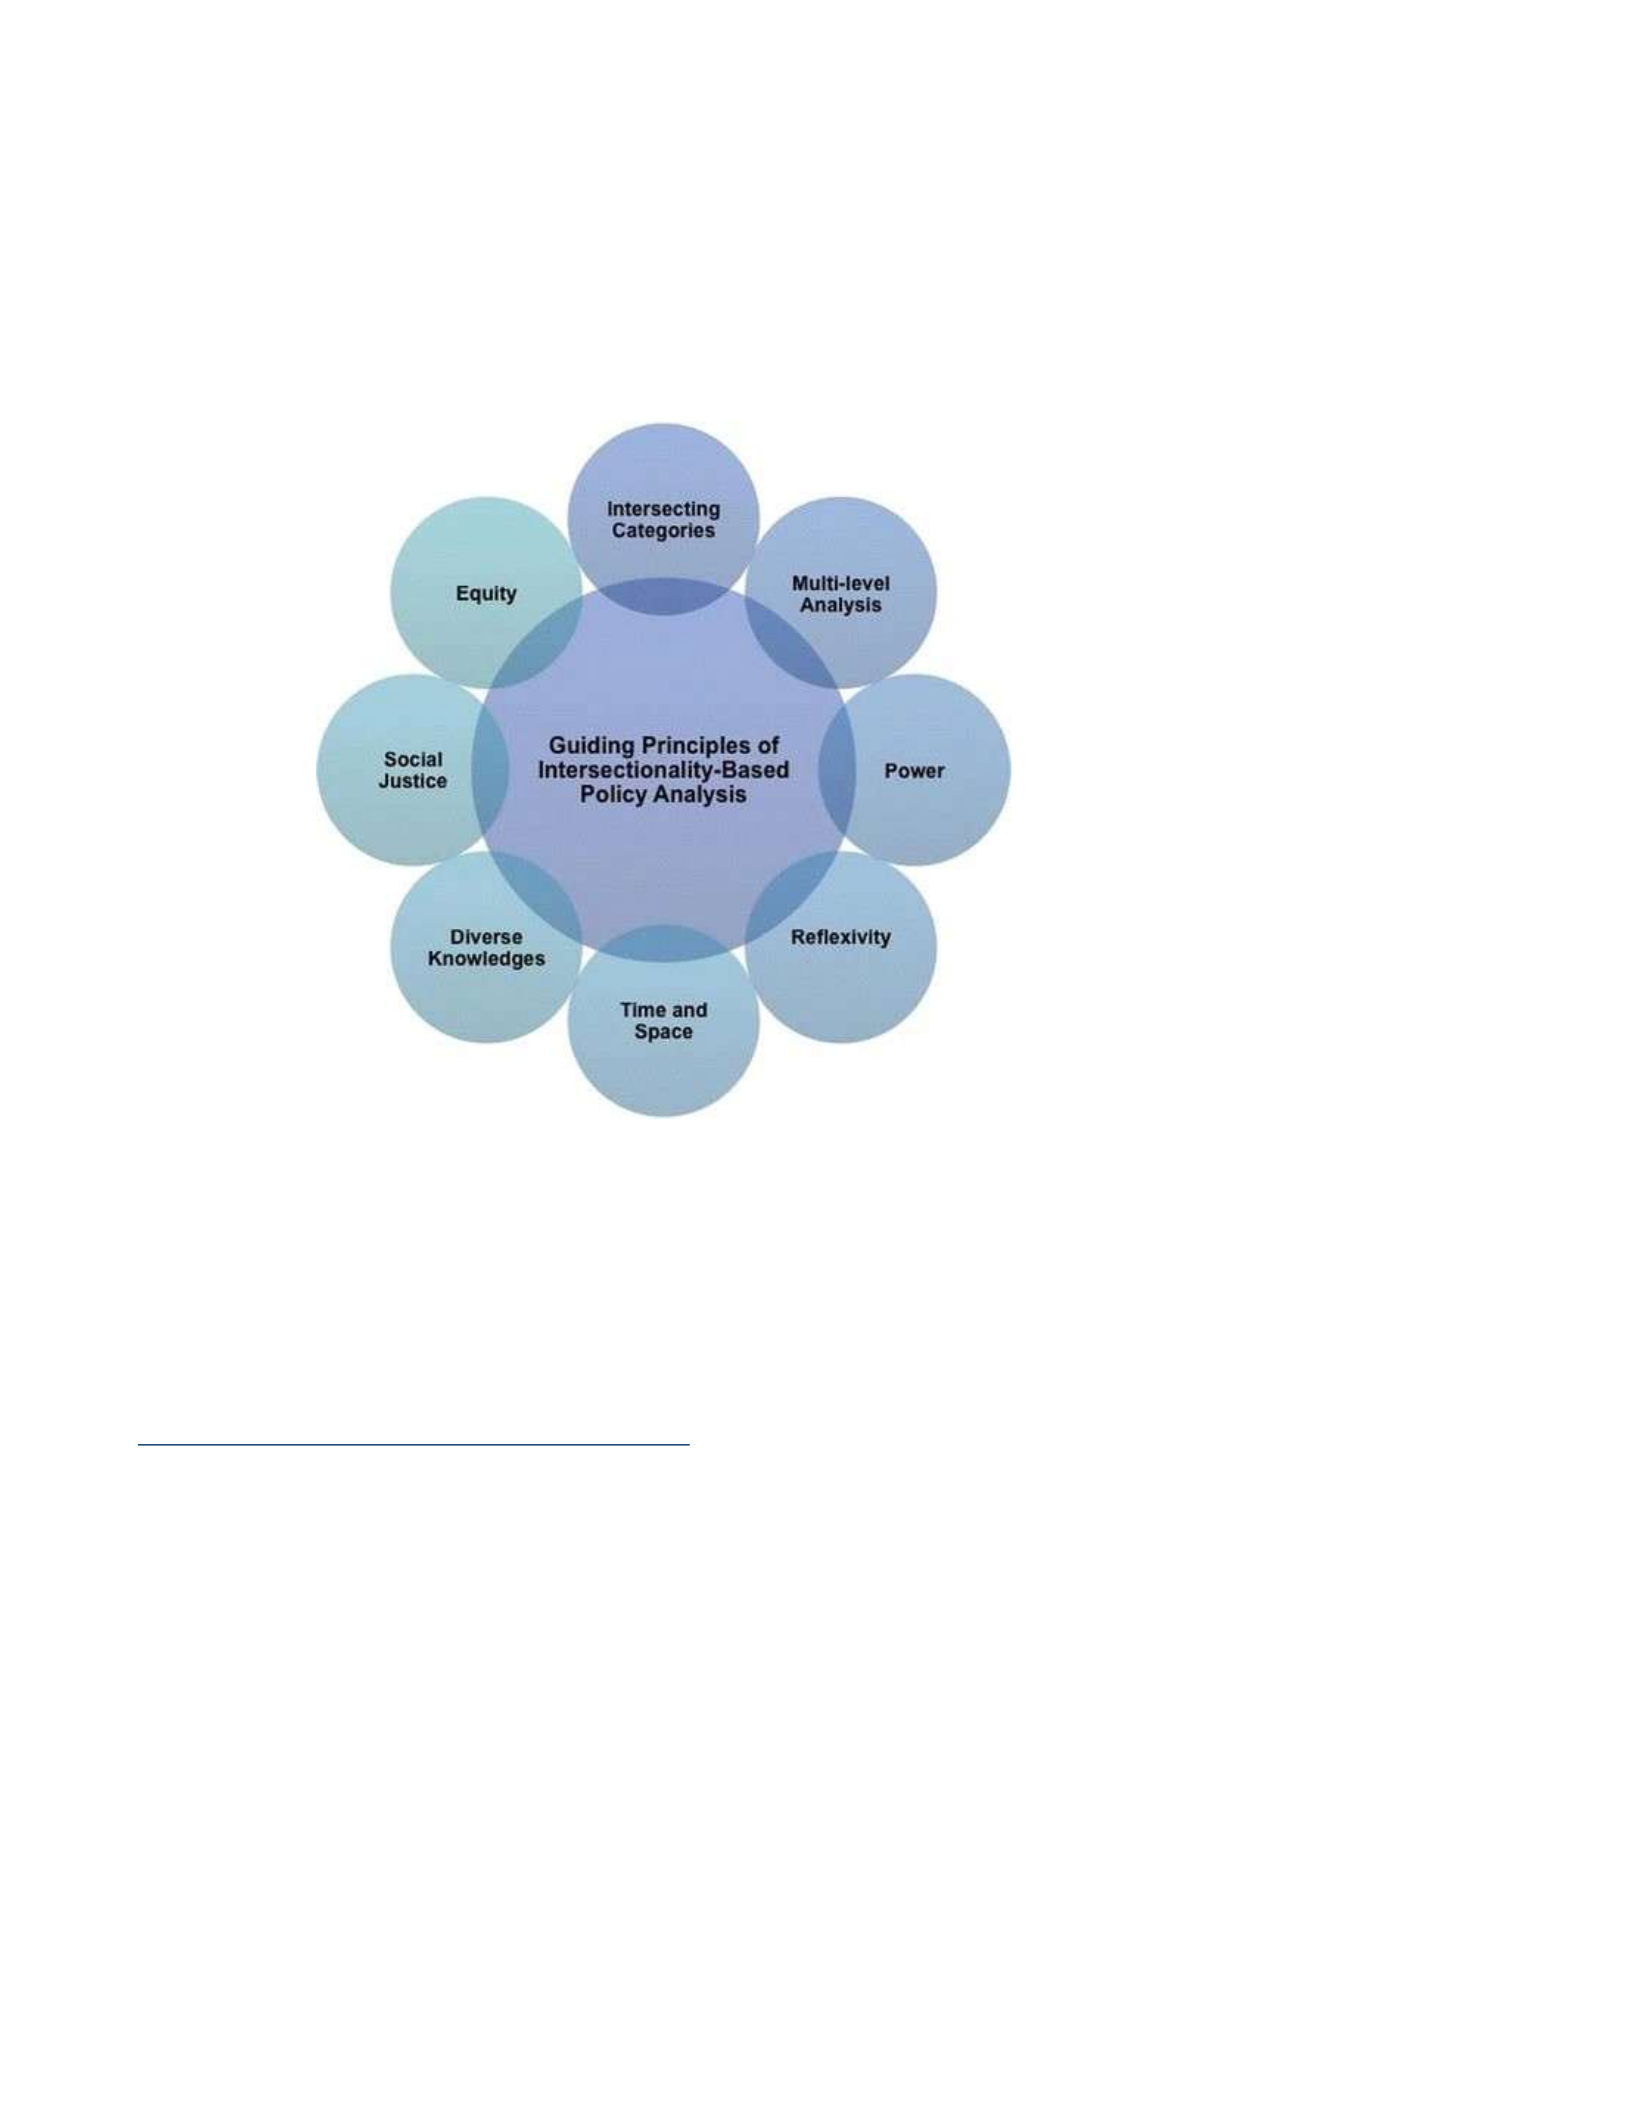
(Hankivsky et al., 2011). Figure 7 shows the guiding principles of the IBPA framework.
40
Figure 7
Guiding Principles of Intersectionality-Based Policy Analysis
Note. From “An Intersectionality-Based Policy Analysis Framework: Critical Reflections on a
Methodology for Advancing Equity,” by O. Hankivsky, D. Grace, G. Hunting, M. Giesbrecht, A.
Fridkin, S. Rudrum, O. Ferlatte, & N. Clarke, 2014, International Journal for Equity in Health,
13 (https://doi.org/10.1186/s12939-014-0119-x). CC BY 4.0.
IBPA has two foundational components, the first being guiding principles that ground the
second aspect, which is the overarching questions that help guide/frame/shape the analysis-
ultimately, both aspects of the framework are needed. There are eight guiding principles of IBPA:
intersecting categories; multilevel analysis; power; reflexivity; time and space; diverse
knowledges; social justice; and equity (Hankivsky, 2012). Intersecting categories refers to

41
intersectionality and the conceptualization of social categories that interact with and co-constitute
to create social locations based on time and place (Hankivsky, 2012). Multilevel analysis refers to
the effects between and across the different levels within society on a macro, meso, and micro
level while addressing inequity and differentiation across the various levels of structure
(Hankivsky, 2012). Power refers to the varying types of power in structural levels and the
processes in which they operate together to shape experiences of privilege (Hankivsky,2012).
Reflexivity refers to acknowledging the importance of power at the micro level and the
relationship with others while recognizing varying perspectives and truths that allow for self-
awareness (Hankivsky,2012). Time and Space in intersectionality speaks to the when and where
in an epistemological lens. Recognizing that time and space are fluid based on individual
interpretations conditioned by social positions and other influencing factors (Hankivsky, 2012).
Diverse knowledges refers to the dichotomy of power and knowledge from various perspectives,
emphasizing marginalized groups relating to how knowledge can disrupt power (Hankivsky,
2012). Social justice refers to challenging inequities and interrogating power and social structure
at the root, all to achieve equity (Hankivsky,
2012). Lastly, Equity refers to fairness (Hankivsky, 2012).
The overarching questions that underpin the IBPA are divided into two categories;
descriptive and transformative (Hankivsky, 2012). Descriptive questions are as follows:
1. “What knowledge, values, and experiences do you bring to this area of policy
analysis?” ( Hankivsky, 2012, p4).
2. “What is the policy problem under consideration?” ( Hankivsky, 2012, p4).
3. “How have representations of the problem come about?” ( Hankivsky, 2012, p4).

42
4. “How are groups differentially affected by this representation of the problem?” (
Hankivsky, 2012, p4).
5. “What are the current policy responses to the problem?” ( Hankivsky, 2012, p4).
Transformative questions are as follows:
6. “What inequities actually exist in relation to the problem?” ( Hankivsky, 2012, p4).
7. “Where and how can interventions be made to improve the problem?” (
Hankivsky, 2012, p4).
8. “What are feasible short, medium and long-term solutions?” ( Hankivsky,
2012, p4).
9. “How will the proposed policy responses reduce inequities?” ( Hankivsky,
2012, p4).
10. “How will implementation and uptake be assured?” ( Hankivsky, 2012, p4).
11. “How will you know if inequities have been reduced?” ( Hankivsky, 2012, p4).
12. “How has the process of engaging in an intersectionality-based policy analysis
transformed the following?” ( Hankivsky, 2012, p4).
Subquestions for Question 12 center on (a) ways of thinking about relations and structures of
power and inequity; (b) ways in which others engage in the work of policy development,
implementation and evaluation; and (c) broader conceptualizations, relations, and effects of
power asymmetry in the everyday world.
Application of Intersectionality Based Policy Analysis Framework
The IBPA framework has been applied in various case studies relating to health policy
(Giesbrecht, 2012; Rudrum, 2012), criminal justice policy (Clark, 2012) and governance

43
(Fridkin, 2012), and so forth. In relation to this particular study, most studies that have used the
IBPA framework are more recent and are based in Canada and other international markets as
such is the case as it relates to health disparities in health policy (McBride et al., 2022; Cook et
al., 2017; Mac-Seing et al., 2020). McBride et al. (2020) used the IBPA to examine a long-term
care (LTC) policy in Vancouver, British Columbia, Canada. The purpose of this policy is based
on the belief that sexuality is crucial throughout all stages of human life. Unfortunately, when an
individual moves into LTC, their sexuality is often overlooked. The LTC policy aims to affirm
individuals in LTC as sexual beings who should be afforded the opportunity for sexual
expressions, respect upon education and consent, and caregivers who provide support where
needed to help reduce harm.
The IBPA framework in this particular study is used to outline the problem within the
LTC policy- which is older adults are not viewed by society as sexual beings and more as a
homogeneous entity (McBride et al., 2022). The framework presents a perfect vantage to
challenge the multilayered constructs of class, sexuality and intimacy in the intersectionality
paradigm. Followed by the how the LTC policy was developed which was established and lastly
to address the potential to address the problem (McBride et al., 2022). Findings revealed that the
development process as well as the construction of the LTC policy do align with principles of
intersectionality as it relates to equity, reflexivity, and diverse knowledges. Overall, the LTC
policy is deemed feasible, equitable and has the potential to effectively address sexual health for
individuals living in LTC.
In line with the principles of the IBPA framework, Cook et al. (2017) analyzed Canada’s
mental health care policies to promote equity in the mental health system. Their study centered

44
on Canada’s self-directed care model, which allows recipients to manage their health care funds,
giving them greater choice in selecting providers and accessing services that support recovery
(Cook et al., 2017). Through panel meetings and structured interviews, the study examined the
process and outcomes of the model, revealing that intersecting factors influenced patient choices
and recovery experiences. Specifically, issues such as individualized resource allocation draining
funds from ethnically specific services, inconsistent acceptance of the recovery model, and
limited service options in certain areas contributed to inequities (Cook et al., 2017). These
disparities, however, could be mitigated by involving peers in the implementation process,
utilizing Indigenous community support, facilitating the purchase of material goods, and
expanding access to services from ethnically diverse clinicians in the private sector—each of
which has the potential to enhance equity within the model (Cook et al., 2017).
Lastly, Mac-Seing et al. (2020) conducted a study consistent with the IBPA framework,
examining Uganda’s pro-disability legislation regarding sexual and reproductive health. Despite
the presence of such legislation, individuals with disabilities continue to experience violations
and denials of their rights. The IBPA framework was used to explore the intersection of sexual
and reproductive health services, legislation, and health policies (Mac-Seing et al., 2020).
Through interviews with 32 men and women with various impairments, two focus groups with
12 hearing and non-hearing impaired individuals, and non-participant observations at seven
health care facilities, the study found that access to sexual and reproductive health services is
shaped by the intersections of gender, disability, and violence (Mac-Seing et al., 2020). The
research also uncovered widespread discrimination in both private and public health care
settings, where individuals with disabilities faced physical, attitudinal, and communication

45
barriers (Mac-Seing et al., 2020). Moreover, the study highlighted the challenges individuals with
disabilities face in exercising their rights and offered multi-level recommendations to address the
inequities in sexual and reproductive health service access. However, the findings also revealed
gaps in the implementation of policies and the delivery of services
(Mac-Seing et al., 2020).
Literature Review Related to Key Variables and/or Concepts
Social Determinants of Health
SDoH) refer to the conditions in the environments where individuals are born, live, learn,
work, play, worship, and age, which impact a wide range of health outcomes, functioning, and
quality of life (Healthy People 2020; U.S. DHHS). More detailed definitions also encompass the
economic and social factors that contribute to individual and group differences in health status
(Braveman & Gottlieb, 2014). To fully understand the extent of SDoH and its connection to
factors such as race, health disparities, and public policy, it is essential for researchers to first
examine the history of SDoH.
History
What currently is known as SDoH can be seen as early as 1865 when the federal
government attempted to address the matter by passing a health law that was known as the An
Act to establish a Bureau for the Relief of Freedmen and Refugees of 1865 (H.R. 51)- the intent
was to give to vulnerable individuals dislodged by the Civil War access to food, education,
employment, housing, and health care (Dawes, 2019). Seven years after the law was introduced
in an effort to address SDoH, the effort was terminated. Officially the first record of SDoH can
be traced as far back as early 19th century, it is during this time Rudolf Virchow, a German

46
Physician began to study the effects of poverty and disease (specifically during the typhus
epidemic) from both a biological and social lens. Even further, his research examined social
inequities as it relates to health outcomes (Lange, 2021) thus laying a foundation for what we
have come to know as public health today. As thinking like Virchow began to evolve and would
eventually become a global focus by 1948. The World Health Organization (WHO) in response
to the humanitarian and public health challenges that arose from WWII defined health as "a state
of complete physical, mental and social well-being" (World Health organization, 1948). The Cold
War and its challenges unfortunately would change the course of addressing social determinants
as it related to health both globally for WHO as well as nationally for the United States.
By the 1960s, there was a noticeable shift as nations in Asia, Latin America, and parts of
Europe began adopting community-based initiatives, such as rural primary health clinics and
community health workers delivering care. These efforts laid the groundwork for the philosophy
of primary care rooted in social medicine, which emphasized the belief that improving
population health required addressing living conditions, such as nutrition, work, and housing
(Lachenal, 2022). This movement culminated in the 1978 International Conference on Primary
Health Care in Alma-Ata, Kazakhstan, which advocated for primary health care for all (Wintrup,
2022). However, many leaders found the declaration too vague or preferred a market-based
approach to health care, which focuses on intervention and achieving timely health outcomes
(Wintrup, 2022).By the 1990s, WHO began to examine health through a macroeconomic policy
lens.
By 2002, WHO established the Commission on Microeconomics and Health; through the
expertise of economist and health analysts, they were able to quantify the impact of SDoH into

47
monetary value (Sachs, 2001). Of the many the results of the report, the most substantial of it
allowed the depiction of need in investiture in health for economic development in the worlds
countries with poor health spans. It also allowed for more substantial goals and objectives that
included SDoH. Since then, the United States has incorporated SDoH-centered care into their
model of care as guided by the first iteration of Healthy People 1990 and every decade since
(CDC, n.d.).
Unfortunately, health outcomes and health spending in the United States continue to be a
dichotomous area of contention especially as health care cost has continued to rise despite health
initiatives such as the ACA (National Conference of State Legislatures, 2021). The ACA was a
comprehensive and inclusive health policy intended to advance health equity amongst all
populations- socioeconomic, racial, age, and so forth. The ACA was the first expansion of
coverage since the enactment Medicare and Medicaid; overhaul of individual insurance market
with more affordable coverage for more people; improved regulations to the employer market
and significant changes to delivery system intended to constrain cost and improve quality. While
the ACA acknowledged SDoH, the individualized efforts of the policy to address low-income
neighborhoods or racial and ethnic disparities were not prioritized for the populations that
necessarily needed it but rather the average Americans (Leong & Roberts, 2013) and as a result
though an innovative policy to advance health care, still a failure for the advancement of SDoH
and addressing health disparities in the United States.
Accelerating to 2019-2020, when the United States saw the rampage of the COVID-19
pandemic, but with it came health care challenges that shook the core of the nation. Economic
security, food security, health care delivery/system, neighborhoods, and physical environments,

48
as well as overall safety, were interrupted/threatened/lost at the height of pandemic more for POC
in comparison to their White counterparts (Drake & Rodowitz, 2022). The pandemic brought to
the forefront SDoH not only as a national discussion but also a global one. It garnered a joint
response from the CDC and CMS a roadmap to improve outcomes, lower costs and support state
value-based care strategies (CMS, 2021). And as a result, federal, state and community
organizations continue to work together to traverse the link between SDoH and health equity.
Racism, Bias, and Discrimination in Health Care Delivery
Having established the history of SDoH, it is easier to lay the foundational history of
health inequities towards African Americans in the context of SDoH. Racism depicts
discriminatory practices maintained through institutional and systemic policies and procedure in
private and public sectors. It often creates a standard that strengthens inequality when
individuals, more specifically POC attempt to access resources that aid in their development and
sustainability of quality of life both individuality and as a group (Bassett & Graves, 2018). That
includes equal access to good quality health care. But research has shown that bias directly
affects health through poor health care, as is the case in the findings put forth by the Institute of
Medicine’s (2003) report Unequal Treatment: Confronting Racial and Ethnic Disparities in
Healthcare. The report also documented the systematic bias experienced by POC which resulted
in substandard care. Bias that has continued to exist despite attempts to improve with
advancements in medical education.
The U.S. health care system has a long history of implicit bias physician bias, as
evidenced by a systematic review which revealed that physicians often project implicit bias onto
minority patients which in turn influences clinical decisions as it relates to diagnosis, treatment,

49
referral and pain management for the minority patient under their care as opposed to their White
counterparts- which could be seen as referral to a specialist or narcotics v. non narcotics etc
(Dehon et al., 2017). And a result of this is often higher morbidities, lack of preventative
management because minority patients has been turned away (Maness et al., 2021) despite an
increased incidence of chronic illness, chronic
pain, worst chronic pain outcomes, and poorer treatment of chronic pain (Mally &
Vallerand, 2018). In comparison to their White counterparts, POC but more specifically African
Americans are more likely to be uninsured; and even those who are, they are still less likely to
use health services unless it’s for emergent services (Adekson, 2021) due to their distrust of
health care and biomedical research (Maness, 2021).
This feeling of distrust is not without reason, as it traces back to a disparaging antiquity.
The history of distrust as it relates to African Americans and health care goes as far back as the
exploitation of enslaved women, who were brutalized with surgical procedures to further advance
gynecology (Adekson, 2021). Another example is the harm done to African American men in
Alabama during the Tuskegee experiments or African American children who were medicated
with harmful drugs to study the propensity of violence (Adekson, 2021). These are just some
examples of the harm the health care community in the United States has inflicted on African
Americans rooted in bias and discrimination that have led to mistrust and fear towards health
care.
The systemic aspect of this discourse, particularly in relation to bias, cannot overlook the
socioeconomic disadvantages that POC, especially African Americans, have historically faced
and continue to experience, such as poverty (Harris & Pamukcu, 2020). These disadvantages

50
have significantly contributed to the poor quality of health care delivery they receive. Regarding
access, predominantly African American/Black communities have historically received less
funding than communities that are more racially mixed or predominantly White (Bailey et al.,
2017). This lack of investment results in disparities in the quality of care, health care utilization,
and access, leading to poor health outcomes for these communities. These disparities are
reflected in the presence of fewer qualified physicians, inadequate promotion of health resources,
and inequitable health care infrastructures. These factors collectively contribute to the chronic
inability of impoverished individuals to control their circumstances, which exacerbates negative
health outcomes beyond the direct correlation between poverty and limited access to basic
resources like nutritious food, clean water, and adequate health care in communities of color
(Harris & Pamukcu, 2020). These issues are closely linked to structural bias, which restricts
access to public goods, services, and opportunities within society (Harris & Pamukcu, 2020).
Public Health Policy
As it relates to public policy, one must acknowledge that historically, what should have
been used as a tool has rather been a determinant of racial inequities in health disparities. For a
county that is such an advocate for individual agency it turns a blind eye to the institution and
structural context in which individuals make choices- especially as we have seen as it relates to
health care. And now as we seek to address the issue of health disparities as it relates to the
context of this study, public policy is one of the many tools being employed to address it.
Pre-Medicaid Era, 1789–1964
While the United Stated health care system has practically been around since the
beginning to the country birth, as it relates to Black/POC in this country, their history was a little

51
different. Initially, Black people for a long time were excluded from the health care system both
as patients and providers. During slavery, enslaved people often had to rely on their fellow
enslaved to assist with medicinal matters- often using what is known today as alternative
medicine (College of Physicians of Philadelphia, 2022), which were Black health care system at
the time. With the emancipation of enslaved persons in 1865, post-Civil War health outcomes
were such that Black people died at 3 times the rate of Whites (. Y. Smith et al., 2021). The first
response to this by the federal government for the Black community was the medical division of
the Freedman’s Bureau- which was authorized by Congress in 1865, but unfortunately due to the
overwhelming need to keep up and the lack of support it came to an end in 1872.
With the Jim Crow era, racism has a huge part in the structure as well as financing of the
health care system as it was known. An example of this was seen as early as the Hospital Survey
and Construction Act or the Hill – Burton Act of 1946 (PL 79-725), which mandated the
construction and modernization of health care facilities, as well as the availability to all without
the consideration of race, but it did allow the construction of racially separate and unequal
facilities (Yearby et al., 2022). As a result, public hospitals in primarily Black communities were
underfunded with less than subpar resources.
Medicaid Era, 1965–2008
The most foundational public policy as it relates to health care systems and delivery is
Medicaid. Created in 1965 during the Civil Rights era, as a derivative of the Social Security Act
Amendment, Medicaid was established as a public insurance program that provides health
coverage to low-income individuals and families (Center on Budget and Policy Priorities, 2020;
Yearby et al., 2022). As a safety-net program, it was intended to continue to oppress communities

52
of color but the paradox of the matter is that it did the complete opposite, but that does not
withstand the inequities that still arose as a result such as Medicaid funding for hospitals, care
facilities.
Today, while states operate their own Medicaid programs, the caveat is operating within
federal guidelines; hence the joint funding by both the federal government and the states. But the
interesting aspect of the federal guidelines is that they have been for the most part extremely
broad with very little details thus giving states a lot of authority as well as flexibility in
designing, administering and delivering their own programs. As a result of that flexibility is
various eligibility and benefits depending on the state. (Center on Budget and Policy Priorities,
2020). An example of this is the push for work-reporting requirements. The argument has
required that this notion will encourages work among able-bodied poor as a condition of
insurance which is based on the assumption that
“Black people are lazy and have poor work ethic”.
As of May 2022, nearly 89,000,000 individuals were enrolled in Medicaid and the
Children’s Health Insurance Program (CHIP) or 81,900,000 in Medicaid and 7,070,000 in CHIP
(Medicaid, 2022). With the passing of the ACA, it made Medicaid the largest public health
insurance provider in the United States (Michener, 2022). On a microlevel, the racial makeup of
individuals that utilize Medicaid highlight the need to address equity as it relates race within
health care: African Americans account for 20% and Latinx account for 30% and other POC
account for 10% (Michener, 2022). But on a state level, especially in major cities POC account
for 65% or more as Medicaid beneficiaries
(Michener, 2022).

53
Because of the socioeconomic difficulties often faced by POC quality and access is
extremely important. But unfortunately, because Medicaid is such a fragmented and
decentralized program, there are many opportunities for inequities to emerge. States have the
right to decide with benfits they offer as part of their Medicaid program such as dental, vision,
physical therapy, and so forth. States can choose which waivers they pursue for things such as
work-reporting requirement or home and community-based services. Terms of provider payments
can be set up through contracts and fee schedules. States can determine how much they invest in
outreach measures and initiatives to ensure eligible individual receive benefits. States can decide
how to manage and oversee program administration (Michener, 2022). Regardless, whatever
policymakers in these states decide in terms of their Medicaid programs it has an implication as
well as social and economic disadvantages for marginalized groups that have been historically
affected.
Patient Protection and Affordable Care Act, 2008–Present
As indicated before, the most significant policy since Medicaid in 65’ was the enactment
of the ACA (PL 111-148). Under the ACA, there are four main payer or sources of health
financing; employers, insurance companies, the federal government and states (Yearby et al.,
2022), unfortunately with the current two-tier health system in the United States, inequities still
remain today. In the case of individual insurance markets were banned from denying coverage
based on risk ratings and preexisting conditions exclusions. As a result, federal subsidies were
offered for individuals between certain income levels (Yearby et al., 2022). These changes made
insurance more affordable in come instance but in most cases, it is always the case especially for
those seeking

54
Medicaid.
Most Americans receive their health care through employer-sponsored insurance,
according to the Kaiser Family Foundation, as of 2019, 58% of Americans were covered by their
employers with a 66% of White covered by insurance, 47% of Black, 43% of Latino, 37%
American Indian and Alaska Native (2021). In the case of low income racial and ethnic minority
who are employed and insured by their employers, they are often left with high out of pocket
premiums and cost sharing, higher than the ACA marketplace. In these instances, they do not
qualify for Medicaid or federal subsidies because they make above the income threshold- a
concept known as the ACA firewall (Yearby et al., 2022). The firewall has unfortunately locked
low wage minority workers into insurance plans with their employers that do not provide all the
needed health protections (Yearby et al., 2022).
The ACA, aimed to expand Medicaid access for individuals under the age of 65 with
incomes below 138% of the federal poverty level (KFF, 2014). According to data,
Medicaid expansion states experienced a reduction in the uninsured rate among POC (Cross-Call,
2020). Since the law's implementation, POC have reported fewer costrelated barriers to accessing
care, with Black individuals specifically noting improvements in having a regular care provider.
However, significant health inequities still persist (Yearby et al., 2022). SCOTUS decisions such
as National Federation of Independent Business v. Sebelius, 567 U.S. 519 (2012) which made
expansion optional for states- but this decision was problematic for southern states who were
already pushing back on the ACA. The decision also reinforced the racial hierarchy and
inequities as it relates to health coverage for Black and Latinos (Yearby et al., 2022). As a result
of that decision, 60% of POC fall into the coverage gap many of who are in southern states.

55
Again, the passage of the ACA intended to try and address some of the inequities
historically experienced in health care, and it also had it shaping as it relates to health care
financing and payment systems. For a long time, the federal government has had a hands-off
regulatory approach especially as it relates to the federal incentives and funding for Medicaid
(Yearby et al., 2022). So, while the ACA expanded coverage, there were no changes the financing
and payer system thus leaving minorities at a disadvantage. The federal incentives do more for
employers- exemption from federal and income taxes, lowering of employer taxes etc - but for
the individual it doesn’t always mean high quality care through the employer at lower cost. And
this is greatly due to the lack of oversight of tax-exempt, non-profit health organizations. Thus,
often time, leaving predominately minorities with poor options for health insurance.
The same lack of oversight can be seen as it relates to Medicaid provider reimbursements
and disproportionate share hospitals payments. Such payments are meant to subsidize
uncompensated care provided by hospitals that serve the uninsured and lowincome individuals
which also include Medicaid recipients (MACPAC, 2021). Federal policy required fair
reimbursement since 1981 when the Social Security Act was amended by Congress (MACPAC,
2016). Despite these efforts, payment have been extremely low and provider participation
continued to decrease thus contributing to low equitable access to high quality care for Medicaid
beneficiaries (MACPAC, 2021, Yearby et al., 2022). Ultimately, disproportionate share hospitals
payment in the bigger picture do not seem to benefit POC of color who actually need help.
The government’s lack of oversight and lack of holding health care systems accountable
for their contribution for inequities continue to hurt POC more than anything. While there is a
push for the transition to value-based payment reforms in various levels of health care systems

56
which look like bundled payments for episodes of care or patient-centered medical homes. But
none of these advancements account for the SDoH related to provider performance, ranking and
payment (Yearby et al., 2022). In fact, providers in a way are being penalized for providing care
for low-income minority people. Penalized by the way they are reimbursed as well as the
regressive tax they often have to pay (Yearby et al., 2022). The reality is that U.S. public policy
has remained color blind, especially as it relates to health policy. The victims in this matter are
low income
POC who receive a poor-quality service from providers and the government alike.
Federally Qualified Health Centers
FQHCs (or CHCs, as they are known today) were first established through adopted policy
known as, Economic Opportunity Act of 1964 under the Johnson Administration (1964-1969) as
part of the War on Poverty, as neighborhood health centers (NHCs; M. Cole et al. 2022). Under
the direction of Dr. C.D Gibson & H.J Geiger, they founded the first NHCs in 1965 in urban
Boston and rural Mississippi, in addition to six centers funded through the Research and
Demonstration Office of the
Community Action Program part of the Office of Economic Opportunity housed in the
Executive Office of Johnson Administration. The centers were designed to provide
comprehensive health care and training and employment services for local residents, based on the
South African community-oriented primary care program Geiger helped developed (M. Cole et
al., 2022). In 1966, the Comprehensive Health Planning and Public Health Services Act (PL 89-
749) authorized funding for health services at the regional and state levels, with Section 314e
offering project grants aimed at developing health service initiatives, including NHCs.

57
Furthermore, Senator Kennedy introduced an amendment to the Economic Opportunity Act,
securing $50,000,000 in funding for NHCs.
By 1971, the National Association of Neighborhood Health Centers was established,
authorized by the Office of Economic Opportunity, with the mission to provide education,
training, and technical assistance to NHC staff and community board members (Geiger Gibson
Program in Community Health [Geiger Gibson], n.d.). This authorization also facilitated the
expansion of NHCs across the country, resulting in the establishment of over 100 federally
funded health centers. A decade after the creation of the first NHC, and following the success of
multiple demonstration projects serving nearly 1,000,000 patients, the federal government, under
the Ford Administration (1974-
1977), made NHCs a permanent program under Section 330 of the U.S. Public Health Service
Act (Geiger Gibson, n.d.). NHCs were subsequently renamed CHCs. The legislation required
CHCs to serve medically underserved areas, specified essential services they must provide, and
mandated that the majority of the governance board members be consumers of the centers'
services. It also categorized services into primary
(required) and supplemental (optional) services (HRSA, n.d.).
Under the Carter Administration (1977-1981), health centers were expanded, especially in
rural areas- doubling funding for the next 4 years (M. Cole et al., 2022). The Rural Health
Services Act (PL 95-210) allowed for rural health centers to be selfsustaining, which was a big
improvement. And it also increased Medicaid and Medicare reimbursements and allowed
payments for services by non-physicians’ providers (Lefkowitz, 2007). But still many of the
services offered by these health centers unfortunately were not eligible for reimbursement by

58
Medicaid and Medicare. By 1978, a bill drafted by Senator Javits that allowed authorization for
hospitals to receive CHC funding for the purposes of primary care- as the current legislation up
until this point because majority of the board members had to be consumers of CHC services.
The bill was part of the amendment to the Public Health Services Act (PL 95-626), with the 3
centers developed in 1980 since the amendment. 1980 also marked the transition from the
Department of Health, Education and Welfare to DHHS and Public Health Services remaining
under the department (DHHS, 2021).
The Reagan Administration (1981-1989) will mark the beginning of threats to the
progress that had been made to CHCs around the United States. Reagan upon his appointment
proposed elimination of federal programs that included CHCs as well as migrant health centers
(which was authorized under Section 329 of the U.S. Public
Health Service Act under the Kennedy administration), but the National Association of
Community Health Centers and its members fight against the Reagan Administration and are
victorious, returning the program to direct federal-local collaboration (Geiger Gibson,
n.d.). At the same time, during the global economic recession from 1981-1983, National
Association of Community Health Centers was able to secure 65,000,000 in funding (20% CHC
annual funding) as well as federal funding for the development of state and regional primary care
associations. During Reagan’s second term, he again threatened to eliminate block grants for
CHCs and migrant health centers. Again, health centers rallied bipartisan support to repeal the
optional block grant options that was being proposed and again to return to direct federal-local
collaboration. It was also by the time, that both state and regional primary care associations had

59
formed to monitor policy developments, receive their first federal funding as well as receive
federal recognition (Geiger Gibson,
2022).
Under Bush Sr. Administration (1989-1993), Bush proposed health center expansion, as
well as increasing federal funding by more than $150,000,000. As a result, Congress authorized
the centralization of health centers’ grants administration, established FQHCs in Medicaid and
Medicare and extended malpractice coverage under the Federal Tort Claims Act. In 1990, the
Public Housing Primary Care Program created under the Disadvantaged Minority Health
Improvement Act of 1990, enabled health centers to provide an integrated approach to primary
care for residents of public housing to address disparities and improve outcomes with increased
access to comprehensive primary health care services through the direct provision of health
promotion and disease prevention activities and primary health care services (NCHPH, 2021).
By 1992, Congress had also created the 340B Drug Pricing Program- which allowed drug price
discounts to also be extended to clinics, health centers, and disproportionate share hospitals to
low income/minority patients for the purpose of providing access to care (HRSA, n.d)- through
the enactment of Veterans Health Care Act of 1992. With the progress made with the federal
government with the passing with laws to further the advancement of health centers, an estimate
of 6,000,000 people had been served at this time (Geiger Gibson, n.d.). 1992, also marked a
transition for the Bureau of Health Care Delivery and Assistance to the Bureau of Primary Health
Care. It was also during Bush Sr. administration that Congress developed a Medicare and
Medicaid reimbursement category for FQHCs (Geiger Gibson, n.d.).

60
Under the Clinton Administration (1993-2001), health centers continued to grow but it
also came with challenges. There were attempts by a very conservative Congress to block grant
or dismantle many health programs that also included Medicaid. But despite the numerous
attempts, health centers secured a 5-year reauthorization to defeat Medicaid block grants (Geiger
Gibson, n.d.). The Health Centers Consolidations Act of 1996 (PL 104-299), reauthorized
funding through 2001 for community, migrant, homeless and public housing health centers
(Health Centers Consolidation Act of 1996, Pub. L. No.
104-99, § 2, 110 Stat. 3626 1996). Congress also established CHIP. By this time,
9,000,000 patients around the country had now been served.
The Bush Jr. Administration (2001-2009) differed significantly from previous
Republican administrations in its strong support for CHCs and health policy initiatives. Bush Jr.
was a prominent advocate for CHCs, and his administration doubled federal grant funding for
these centers, expanded 1,200 facilities, and increased health care access for 6,100,000 additional
patients, meeting their goal (Geiger Gibson, n.d.). As a result, the total number of people served
by CHCs since their inception reached 18,000,000. The administration worked to protect and
increase CHC funding, including the 2002 Health Care Safety Net Amendments (PL 107-251),
which reauthorized and raised funding levels through 2006. In 2008, Bush further supported
CHCs by signing the Health Care Safety Net Act of 2008 (PL 110-35), reauthorizing and
increasing funding for the program until 2012.
The Obama Administration (2009-2017) since before his campaign, advocated and
endorsed health centers and its expansions as a public safety net. Upon his appointment,
Congress reauthorizes and renames CHIP, expansion reached 4,000,000 additional children and

61
incorporated FQHC payment rules. The American Relief and Recovery Act of 2009 appropriated
over $2,000,000,000 for expanding centers as well as upgrading the technology in these health
centers. Also, the American Reinvestment and Recovery Act of 2009 did provide $2,000,000,000
in direct CHC funding for new patients, capital expenditures for expansions as well as
$300,000,000 for NHSC, Medicaid funding expansion that included assistance to health centers
approaching an additional $1,000,000,000 for health information technology adoption (Geiger
Gibson, n.d.).
With the passing of the ACA in 2010, health reform became the theme with the federal
government. This landmark passage allowed for health care centers to expand access, improve
quality and reduce cost for all Americans. Additionally, the passage provided $11,000,000,000 in
increased CHC funding all the way through 2015 to enable health centers to double capacity as
well as $1,500,000,000 for the National Health
Service Corps to for 5 years to expand clinicians in underserved areas (Geiger Gibson,
n.d.). With the shift in control of House after the 2010 elections, there was now a push to reduce
the federal budget and repeal health reform. To address the $14,000,000,000,000 Federal budget
deficit, House proposed cuts in domestic spending, block granting
Medicaid, and reduction/elimination of many domestic programs. At the conclusion, the
2011-2012 federal budget eliminated $600,000,000 in funding from CHC programs and
$125,000,000 from NHSC- which allowed down the health center expansion as promised by
Obama and the National Association of Community Health Centers. But despite this temporary
defeat, under 20,000,000 people served by CHCs as of 2011.

62
Even with the loss of funding, health centers around the country continue to grow. By
2013, more than 22,000,000 people had been served in over 9000 medically underserved
communities (Geiger Gibson, n.d.). But due to the political back and forth, CHCs were forced to
ensure a 2% reduction in health center funding just in case a sequester went into effect at any
time for a year. By the following year, through the health insurance exchange, millions attained
health coverage, many for the first time. Fiscal Year 2014, secured $3,700,000,000 in health
center funding, which included $350,000,000 for access points, expanded Medical capacity and
service expansion activities and $58,000,000 for outreach and enrollment (Geiger Gibson, n.d.).
But unfortunately, 62,000,000 people were still left without insurance- issues relating to poor
access, and physician shortages. Obama allocated $8,100,000,000 over the course of the
2016- 2018 fiscal years to address the funding cliff for health care centers. The Center for
Medicaid and Medicare Services would also authorize the final rules for the new
Medicare FQHC PPS (Centers for Medicare & Medicaid Services, 2014). 2015 marked 50 years
of the CHC movement, and also the passage of the Medicare and CHIP Reauthorization Act of
2015 which primarily tackled the primary care funding cliff, extended CHC funding for 2 years
with $7,200,000,000 in mandatory funds, provided extension funding for the NHSC and
extended the CHIP program.
The Trump Administration (2017-2021) had to deal with the results of the 2017 hurricane
season as catastrophic as it was, would bring many health challenges to many states and
territories of the United States, thus leaving CHCs at the front lines. With many funding coming
to meet its expiration dates during this time, Congress passed continuing resolutions and
extensions for various things such as the Community Health Center Fund which received a

63
continuing resolution in 2017 with an eventual budget that allowed funding for 2 years in 2018.
CHIP was also extended for another 10 years and additional funding that was allocated towards
disaster relief and recovery as well awards by the way of funding to assist states and territories
with hurricane relief (Geiger Gibson, n.d.). At the onset of the global health pandemic, CHCs
once again played a critical role, offering services such as drive-through and curbside testing,
telemedicine, and adapting facilities to ensure safety. However, the pandemic led to significant
revenue losses, site closures, reduced non-COVID-related services, and staff layoffs, resulting in
an estimated $4,000,000,000 loss over 8 months (M. Cole et al., 2022). While
Congressional relief efforts, including the Paycheck Protection Program (PPP), HHS Provider
Relief Fund, HRSA Uninsured Claims Fund, and supplemental COVID-19 grants, provided some
short-term financial support, the aid fell far short of addressing the full extent of the financial gap
(Geiger Gibson, 2022).
Now under the Biden Administration (2021-), they’ve recognized the importance of
Health Centers especially in light of the pandemic. With the American Rescue Plan Act of 2021
allocated $7,600,000,000 to CHCs to respond to COVID-19 plus the
$5,700,000,000 allocated to CHCs through the Consolidated Appropriations Act of 2021 (Geiger
Gibson, 2022.). The funds were intended boost health resources for testing and vaccination,
workforce and infrastructure. In addition to funding for NHSC, the Nurse
Corps, and the Teaching Health Center Graduate Medical Education programs (Geiger Gibson,
2022). Placing an emphasis on the recognition for their quality and contribution to health care.
As of 2021, there were 1400 FQHCs in the United States that provided affordable
primary and preventative care on a sliding fee scale to nearly 29,000,000 patients (HRSA, 2021)

64
58% of those patients were POC and 68% were either at or below the federal poverty level (M.
Cole et al., 2022). “FQHCs are distinguished by the following components: they are located in
medically underserved areas, they offer comprehensive services, they are open to anyone
regardless of insurance status or ability to pay and they have patient-majority governing boards;
they must also qualify for funding under Section 330 of the Public Health Service Act; offer a
sliding fee scale; qualify for enhanced reimbursement from Medicaid and Medicare” (M. Cole et
al., 2022; HRSA, 2021). FQHCs employ more 225K people and create an average of
$63,400,000,000 a year in economic activity (National Association of Community Health
Centers, 2021).
Promotion of High-Quality Care and Patient Empowerment
FQHCs and other CHCs like them serve to offer more than primary and behavioral health
services for patient needs. To show that, M. Cole et al. (2022) modified Maslow’s hierarchy of
human needs to consider the determinants of health that impact individuals from being their most
health self as well as taking into consideration lessons from the pandemic. M. Cole et al.
proposed that physiologic and safety needs merge, as one cannot be addressed without addressing
the other. Therefore, the same logic applies with FQHCs, while addressing patient needs health
centers while prompting pride and resiliency as well as elevating principles of social justice and
equity in the communities they serve (M. Cole et al., 2022). Thus, going above and beyond to
promote high quality care.
WHO (1998) defined patient empowerment as a process in which individuals gain greater
control over decisions and actions that affect their health. It is crucial for patients to not only
comprehend their care but to actively engage with it, enabling them to become advocates for

65
themselves, not just with their PCPs but across the entire health care spectrum. Patient
empowerment also encompasses the concept of patient-centered care, where patients feel
respected, their choices and contributions are heard and valued, and, most importantly, they are
listened to throughout the care process. It is through these actions in which FQHCs and other
CHCs can add to supports, resource, and opportunities that make a difference in the lives of the
patients that are served (M. Cole et al., 2022).
Together with providing care and meeting social needs, FQHCs have the opportunity to advocate
on behalf of marginalized groups by the way of storytelling the adversity faced specifically by
their patients.
Integrated Care Models for Federally Qualified Health Centers
Integrated Behavioral Health Care
Integrated behavioral health care is a very integral component of FQHCs. Thanks to the
expansions of the ACA the care coordination between the PCP, psychiatrist, and community
support is one that has the potential to improve outcomes. But the reality remains that
coordinated care as it relates to behavioral health and primary care still has a long way to go.
Integrated care has the potential to decrease emergency room use as well as inpatient psychiatric
care (Tepper et al., 2017). Integrated care also has the potential to be the best tool for patients in
settings such as FQHCs especially when patient experiences are taken into consideration.
Related to the current study, Siantz and Henwood (2020) conducted a qualitative study to
assess to understand patient experiences as well as provider perceptions of patient experiences as
it relates Behavioral Health Integration and Primary Care through a system that delivers
integrated care to patients with co-ccuring disorders. Siantz & Henwood identified 54 patient

66
participants above the age of 18, and 32 provider participants in which they described how
patient experience with care changed under the initiative in focus groups (eight patient focus
groups, five provider focus groups). Patient experience and provider perception of patient
experience aligned under two themes- care coordination being essential for positive patient
experience and the integration initiative strengthening patient provider relationships. Perspectives
were different as it related to patient experiences with programming. One main limitation of the
study was the fact that it was done in California this limiting the generalization of the study. But
overall, the results did highlight the importance of including patient experience into the redesign
of integrated care systems as well as the importance of PACs to ensure quality improvement
(Siantz & Henwood, 2020).
The primary care setting has increasingly become the entry point for addressing
behavioral health needs, making it essential for facilities like FQHCs to enhance the continuum
of care. The Center of Excellence for Integrated Health Solutions (2021), funded by SAMHSA
and operated by the National Council for Mental Wellbeing, serves as a valuable resource for
individual practices and clinics, helping to customize approaches to achieve integrated care.
While the benefits of integrated care are clear, it is important to also consider the challenges.
Integration is not a one-size-fits-all solution, and without sufficient funding, there is little
incentive to pursue integration due to the associated costs (Deis, 2020). Additionally, policy
barriers complicate financial management, as payment policies remain inadequate, and issues
related to billing and technology for consultations further hinder integration efforts (Deis, 2020).
One successful approach to integrated behavioral health care is the evidencebased
strategy developed by University of Washington researchers and practitioners known as

67
collaborative care (AIMS Center, n.d). CoCM is a "specific type of integrated care that treats
mental health conditions that require systemic follow-up due to their persistent nature. Based on
the principles of effective chronic illness care, CoCM focuses on defined patient populations
tracked in a registry, measurement-based practice and treatment to target” (AIMS Center, n.d.).
PCPs and behavioral health professionals collaborate to provide evidence-based treatment and/or
medication supported by case consultation and treatment adjustments for patients who are not
improving as expected (AIMS Center, n.d.). The core principles of the CoCM model are that it is
patient centered and population centered care; treatments to target are based on on-going needs
until clinical goals are achieved; evidenced based care; and lastly accountable care- providers are
held accountable and reimbursed for quality of care and clinical outcomes (Little & Epp, n.d.).
The model embraces the idea of one access site in which a patient can receive comprehensive
care, which in turn increases both patient engagement and satisfaction with their health care
(AIMS Center, n.d). The CoCM model embraces Evidence has also shown that this approach is
effective in addressing SDOH with marginalized groups in FQHCs.
Reising et al. (2022) conducted a qualitative study to examine the implementation of the
CoCM, a type of integrated behavioral health, at an FQHC in Humboldt Park, Chicago. The
study aimed to address Social Determinants of Health (SDoH) and reduce health inequities in
this marginalized community. To better understand community needs, the researchers assessed
the SDoH affecting the population by utilizing Healthy People 2030 objectives. The assessment
revealed significant disparities, particularly in education, employment, health care access, and
neighborhood safety. For example, the community had "lower high school graduation rates,
limited employment opportunities, and over 20% of residents had limited English proficiency"

68
(Reising et al., 2022). Access to health care was also limited, as over 20% of residents lacked
insurance, and although there were several CHCs, gaps in health care access remained evident.
Furthermore, the neighborhood faced high crime rates, limited access to healthy food, and higher
housing costs compared to other parts of Chicago. Economic and physical health data indicated
that residents experienced financial and food insecurity, lower life expectancy, higher chronic
illness rates, and increased substance use compared to the broader Chicago population (Reising
et al., 2022).
Based on these findings, Reising et al. (2022) selected an FQHC in Humboldt
Park to implement the CoCM, supported by the University of Washington AIMS Center. Before
the study, the FQHC operated under a traditional primary care model, and behavioral health staff
were not involved in collaborative care management. Between July 2019 and July 2020, the
study served 1,213 patients. The collaborative care team included PCPs, including nurse
practitioners), a behavioral health consultant (BHC) who was also a licensed social worker and
certified in drug and alcohol counseling, a psychiatric consultant (psych nurse practitioner), an
RN, a registered dietitian, a clinical pharmacist, and medical assistants. Importantly, the team
reflected the racial and ethnic diversity of the patient population, which consisted of 41% Black,
34.5% Hispanic,
15.4% White, and 9.1% Asian, multiracial, or individuals who preferred not to disclose. Of the
patients, 54% were men, 46% were women, and most were covered by Medicaidmanaged care
plans (Reising et al., 2022).
During each patient visit, behavioral health screenings were conducted using the Patient
Health Questionnaire and Generalized Anxiety Disorder tool. Patients who screened positively or

69
expressed behavioral health concerns were introduced to the CoCM and offered behavioral
services. Those who consented underwent a comprehensive assessment by the BHC, who then
developed a personalized care plan. Patient progress was monitored through regular screenings
during each visit. The psychiatric consultant collaborated with the BHC and PCPs to optimize
treatment and medication management, while multidisciplinary team meetings were held
biweekly to discuss patient care. The BHC also provided care coordination and referrals for
addressing financial, social, and emotional needs, such as food resources, transportation, and
employment (Reising et al., 2022).
Reising et al. (2022) used several outcome measures to evaluate the implementation of
the CoCM: access to behavioral health and medication-assisted treatment for opioid use disorder,
pre- and post-treatment Patient Health Questionnaire and Generalized Anxiety Disorder scores,
primary health care outcomes, and access to nutrition counseling and food resources. The results
indicated that patients experienced improvements in both depression and anxiety scores. Patients
receiving medicationassisted treatment averaged 7.2 visits, which included primary care and
buprenorphine management. The intervention also facilitated the development of stronger
relationships between patients and their care teams, immediate connections to food resources
through the dietitian, and effective care coordination by the BHC that ensured access to
community-based resources tailored to each patient's needs (Reising et al., 2022).
Despite these positive findings, Reising et al. (2022) acknowledged several limitations.
The implementation of CoCM at a single FQHC limits the generalizability of the outcomes, and
the study was also affected by challenges related to the global pandemic. Nevertheless, the
findings underscore the potential benefits of integrated behavioral health care for marginalized

70
communities. Further research is necessary to understand how integrated behavioral care can
address specific SDoH affecting African Americans and to explore how these outcomes can
inform health care policy to improve health outcomes for African Americans in the United States
(Reising et al., 2022).
Culturally Centered Integrated Care
Culturally centered integrated care (CCIC) is an approach to health care that take into
consideration the cultural beliefs, practices, and values of individuals and communities being
served (Betancourt et al., 2003). It aims to provide care that is both respectful and responsive to
the unique needs of culturally diverse populations with the goal of improving patient outcomes
and reducing health care disparities (Betancourt et al., 2003). In order for CCIC to work there are
key elements that are pretty important, such as understand the cultural and linguistic needs of
patients, building partnerships with CBOs and providing culturally competent care (Zeh et al.,
2012). Evidence also suggest that CCIC can be especially beneficial for diverse populations, who
may face unique cultural and linguistic barriers to accessing health care. The authors argue that
CCIC can improve health outcomes and reduce health care disparities by considering cultural
factors such as language, religion, and traditional healing practices (Dower et al, 2017; Zeh et al.,
2012).
In a systematic review done by Anderson et al. (2014), the focus of study was 0n the
importance of cultural competence in health care which is a key component of CCIC. They
researchers examined the effectiveness of CCIC interventions when improving health care
outcomes for diverse populations, more specifically minority and immigrant populations. The
authors found that CCIC interventions are associated with improved patient satisfaction,

71
increased prevention services and reduced health care cost. But more research was needed to
understand the impact of CCIC on health care outcome.
Wrenn et al. (2017) conducted a study to introduce a cultural perspective to the literature
on integrated care for addressing depression and co-occurring chronic health conditions in
primary care. The study involved 32 adult patients from an integrated primary care clinic who
participated in focus groups discussing their health experiences. Key themes included peer
support and community engagement. Participants had a good understanding of depressive
symptoms but lacked knowledge about treatment options and expectations. The researchers
concluded that "integrated care models developed to improve care among underserved minorities
should focus on increasing the engagement of African Americans at risk for depression," and
emphasized culturally tailored systems that promote education, community involvement,
compassion, and minority participation in care (Wrenn et al., 2017).
Justification for a Qualitative Study
The use of an exploratory qualitative approach for this study was the first choice. As it
relates literature around integrated behavioral health care, many studies, especially within the last
5 years have used this approach. It should be noted that I did not find a significant number of
studies that used other approaches; therefore, this approach was in alignment with my
phenomenon—implementation of CIBHC. Typically, an exploratory qualitative approach allows
for a phenomenon to be explored with little to no prior research, and for studies which do not
typically require a hypothesis (Rendle et al., 2019). My aim is to understand the phenomena
through the lived experiences of the participants in the study so that I may gather a finding(s) that
can contribute richly to the area of study

72
(Rendle et al., 2019) and potential policy development.
Summary and Conclusions
The importance of this study is to understand the implementation of culturally appropriate
integrated behavioral health care as it relates to the health care access and quality for African
Americans from a public policy lens. Considering the African American community history with
of disparities as it relates to health care institutions, the public health policies of past and present
have not always been fair nor considerate of the groups pain. To truly erect a meaningful public
health policy, is to truly acknowledge, understand and address the issues experienced by the
African American community. In this chapter, I examined the foundations for the study,
reviewing literature about SDoH, public policy and integrated care, objectively and analytically.
The literature review highlighted the integral part of the history that relates to the inequities in
the U.S. health care delivery system as it relates to African Americans; indicating the need for
their involvement in health care policy.
Conversely, very few empirical peer-reviewed studies address the phenomenon of CIBHC
implementation that considers health care access and quality, lending justification for this
research to fill this significant gap. While there have been reports, medical studies, and peer
reviewed literature that had addressed integrated care, an irresistible gap remains, which fails to
deliver the perspectives of African American patient qualitatively.
It was problematic to find current/recent peer-reviewed studies that aligned with my problem.
Researchers have also done little to qualitatively address determinants that factor into the health
care delivery system’ disparities faced by the African American community and whether the

73
implementation of CIBHC that considers access and quality affects increases health outcomes
from a public policy lens.
The reemerging themes throughout this chapter-social determinants, access to good
quality health care, and a failed health care system delivery specifically for the African American
community. Another common theme was health inequities and its relation to that of African
Americans/POC being less likely to receive proper quality care in comparison to their White
counterparts despite the advancements made in health policy. The information presented from
this chapter from various studies provide a consistent theme on how health inequities has affected
the African American community in various ways, thus a problem with public health policy.
Addressing iniquitous health care delivery as it relates to the African American
community is critical to improving health outcomes and therefore the quality of life of
marginalized groups overall. Continuing to explore this phenomenon may influence positive
public health policy that benefits marginalized populations. The research gap may shrink through
exploring participants experiences and understanding in their own words how the implementation
of culturally integrated behavioral care is beneficial for them. By paying attention to these details
that it will make it more meaningful to the contribution of policy changes that contribute to social
change within health care. In
Chapter 3, I will outline the research methodologies aligned with the presented problem in my
intended study, the purpose statement, the research question as well as the procedures and
instruments. I will also cover the rationale, methodology, trustworthiness and instrumentation
that will be used for the study.

74
Chapter 3: Research Method
Introduction
The purpose of this qualitative study is to understand the implementation of CIBHC as it
relates to the African Americans experience while taking into consideration health care access
and quality (SDoH), from a public policy lens. The African American community’s relationship
with health institutions in the United States, past and present, and health inequities within this
marginalized community has unfortunately been a negative one. By researching CIBHC and the
intersection of SDOH that affect health outcomes and presenting lived experiences and
perspectives of individual members of the African American community, I hope to bring forward
policy options that support health equity which have the potential to result in improved health
outcomes. It is also an objective of this study to influence the promotion of health care delivery
from a sociopolitical lens that benefits marginalized groups such as the African American
community. Chapter 3 entails the research method employed in this study, the research design,
the rationale, the instrumentation, the data collection and the data analysis process used. The
section also covers a description of the participant recruitment and sampling strategy that will be
used for the study. I will also address the potential biases, ethical concerns and all other issues of
trustworthiness that could come up in the study.
Research Design and Rationale
I sough to answer the following research question in this study: What do African
Americans think about the impact of CIBHC on their own health outcomes and health care
delivery for POC? The central concept or phenomena of this study is the implementation of
CIBHC in the FQHCs as perceived by African Americans. CIBHC refers to high-quality,

75
coordinated health care a patient experiences due to a team of primary care and behavioral health
clinicians working with patients and families, using a systemic and cost-effective approach to
provide patient-centered care for a defined population. This care may address mental health,
substance abuse conditions, health behaviors (including chronic medical illness), life
stressors/crises, stress-related physical symptoms, and ineffective health care utilization patterns
(Academy for Integrating Behavioral Health and Primary Care, n.d). It is also a type of care that
values cultural humility (Mosher et al., 2017) among providers, implementation in physical
environments that respects and appreciates patient diversity and respect other cultures, as well as
considerations that the patient-provider dynamic is a partnership that emerges from centeredness
and empowerment (Holden et al., 2014).
The conceptual foundation of this study is rooted in IAD framework with elements of the
health equity framework and IBPA framework. The conceptual foundation helps positions the
importance of health inequities experienced by African American that exist within the health care
as well lay a foundation necessary to address the matter that is beneficial not only for those
marginalized but also in the larger context of public policy.
For this study, I intend to use a qualitative exploratory inquiry to explore and describe the
experiences of African Americans as it relates to health disparities as well as the effects of
implementation of CIBHC. Creswell (2007) stated that qualitative research is a practical
approach to collecting participants lived experiences through their lens.
Qualitative research allows for collecting descriptive data such as the lived experiences of
African American who have been victims of health disparities in the United States, as well as the
effects of implementing CIBHC in their FQHC where they typically receive care, while

76
accounting for the SDoH that influence their care. Qualitative inquiry not only allows for
participants to explain in their own words their lived experienced but it also allows a systemic
process to collect information (Creswell, 2014). A quantitative approach would not have been the
best design since it is an approach that relies on numerical data (descriptive) to examine the
relationships of variables (Creswell, 2014). The chosen design, as an exploratory
methodology, can be used to focus on the commonality of lived experiences within a particular
group and build on past experiences. The methodology allows for the proper interpretation of
themes, thus making it easier for the researcher to construct a universal meaning of a
phenomenon, in the same reasoning understanding the challenges, motivations and cultures of
the environment. In this particular study, an exploratory qualitative approach, will be used to
identify and interpret African American patient experiences as they relate to health disparities
and their experiences in combinations with the implementation of CIBHC.
Role of the Researcher
Ravitch and Carl (2016) emphasize that in any study, the researcher plays a critical role as
both the instrument of inquiry and the tool for data collection, analysis, interpretation, and
reporting. Additionally, the researcher is responsible for maintaining ethical standards, ensuring
the trustworthiness of the study, and safeguarding the study's validity (Creswell & Clark, 2018).
It is also essential for the researcher to consistently align with the study's purpose and objectives
throughout the research process.
Understanding the world from the participants' perspective is a key responsibility (Creswell &
Clark, 2018). In qualitative research, establishing trust is crucial, especially when collecting
personal and confidential information (Walden University, 2010). Adhering to ethical guidelines

77
ensures objectivity, rigor in data collection and analysis, and the accurate communication of
findings.
The setting for this study will be a FQHC in New York. I am aware of my own affiliation
with this organization, that affiliation being a close relative is one of the PCPs at the facility. Due
to that relation, and to avoid the possibility of a conflict of interest, the researcher does not intend
to include patients from their workload in this study. My background as an African American
woman health professional with over 16 years of experience adds credibility to the eventual data
and findings of this particular study. As it pertains to the matter of bias in a qualitative study,
Ravitch and Carl (2016) stated that the researcher has a duty to self-interrogate their beliefs,
assumptions, biases, interpretations, and conclusions. While bias is likely and anticipated, the
researcher intends to pay careful attention by monitoring her own personal feelings and
identifying where she might insert her own perception the analysis. The use of a research journal
will be employed to help in the monitoring of this process.
I conducted semistructured, descriptive interviews to gain understanding of participants
experiences, which will be pre-checked by a colleague who is a certified health equity subject
expert to ensure interview questions are pertinent, aligned, and biasfree, thus providing expert
validation. In research, expert validation is defined as seeking the opinions and feedback of
experts in a relevant field to ensure the accuracy, rigor, and credibility of a study’s findings
(Boateng et al., 2018). Expert validation can also help identify potential biases, limitations, or
flaws in the research design and methods as well as to make suggestion for improvement
(Boateng et al., 2018)). The method of utilizing expert validation ensures quality and validity of
research as well as improving the rigor and accuracy of findings (Boateng et al., 2018). As it

78
relates to this particular study, the use of the subject matter expert (SME) helps to provide a
deeper understanding of the context and cultural nuances of the particular topic of this study in
relation to the analysis of the eventual data. The subject expert will also help identify potential
biases that may lead to alternative perspectives in which questions are asked, especially since this
is a sensitive topic as well as better clarity on interpreting and analyzing more accurately.
MethodologyParticipant Selection Logic
The target population for this study is African American residents from NYC, due to the
diverse populated city, the likelihood of the intended participants is higher. For the purpose of
this study, including Long Island or the rest of New York State reduces the likelihood of African
American participants and most of the state's Black population resides in NYC (Census, 2021).
The age requirement for this study will be between 18 and 75 years old, the justification for that
is because the FQHC has a senior population that also receives behavioral health care and it does
not seem right to exclude them in case they are interested in participating in the study. The
justification for keeping the upper age limit for this study is because of the higher rate of
cognitive ailment such as Alzheimer’s and dementia more prevalent in individuals 75 or older
(Alzheimer’s Association, 2023). Participants will also need to have a history of receiving
behavioral health care from one of the targets FQHC locations, to be specific, participants will
need to have seen a behavioral health provider at least six times. The justification for the
minimum number of visits to a provider is to establish this is a patient who has received a
diagnosis, and is receiving continuous and ongoing care. This study will utilize a qualitative
approach that seeks to understand what patients think about the impact of CIBHC on their own
health outcomes as well as their thoughts about health care delivery for POC.

79
The sampling method best in alignment with the study is purposive sampling.
Purposive sampling is useful in studies for diverse populations (Martinez-Mesa et al., 2016). As
it relates to diversity with the selected population within NYC, the African diaspora typically
includes people of African origin living outside of the continent, irrespective of their citizenship
and nationality (The African Union, 2003). And while the general selection for race in NYC
might be Black or African American, the reality is many are often of African American, Afro
Caribbean, Afro Latin American, Black Canadians, Siddis, and Africans. Hence the justification
of keeping the population choice to just African Americans. The sampling criteria are as follows:
• being an African American;
• Being between the ages of 18-75;
• Reside in NYC;
• Received a chronic behavioral health diagnosis (a minimum of six visits);
• and be a current or previous patient of an FQHC located in Bedford
Stuyvesant, Brooklyn, New York.
In qualitative research, data saturation occurs when the data begins to reveal similarities
or recurring themes (Glasser & Strauss, 1967; see also Creswell, 2014). Achieving data
saturation indicates the comprehensiveness of the study and ensures that the findings accurately
represent the experiences and perspectives of the participants. Saunders et al. (2017) suggest that
saturation in qualitative research should be approached in a way that aligns with the theoretical
framework while maintaining coherence and rigor. Creswell and Plano Clark (2011) recommend
a minimum of three participants for qualitative studies, while Marshall et al. (2015) suggest that
6 to 10 participants are appropriate. Given the qualitative nature of the study, I strove to recruit at
least 20 participants or at least enough participants to ensure data saturation.

80
A preidentification process will occur with the FQHC to provide the number of current
patients that fit the criteria, which will give the researcher a population size; conformation was
received from the CMO who confirmed that the EMR can generate a list based on the criteria. I
created a flyer containing a brief description of the study, participant criteria, potential benefits of
participation, a brief summary of what participation in the study would entail, and my contact
information (see Appendix A). The FQHCs will help to advertise the flyer on their e-bulletin
boards, their website, social media, and mail that will be sent out to current and former patients’
homes- all of which has been conformed with the CMO of the organization. Once potential
participants respond with interest, the researcher will contact them and schedule a day and time
for
the interview session. Prior to the session, an email with the informed consent and the overview
of study will be sent to participants in which they will have the option to reply with I consent or I
decline which will serve as an electronic signature.
Instrumentation
I followed an interview guide (see Appendix B) to collect data. For the purpose of data
collection, face-to-face, semistructured, descriptive interviews, with open-ended questions, were
used (see Rubin & Rubin, 2012). The interviews were audio recorded via an iPad. Patton (2015)
stated that interviews are the most reliable means of knowing the feelings and thoughts of
interviewees. As it pertains to face-to-face interviews, it allows opportunities for probing by
asking follow up questions to fill up gaps or grey areas. I based the interview guide on the
literature related to integrated care implementation in FQHCs settings.

81
Interview questions will be developed by the researcher and reviewed by the SME from
the perspective of the interviewee to determine how the participants might perceive the questions
being asked. The interview protocol will be used to prepare for and guide the interview process
as well as facilitate the readiness of the interviewer-interviewee dynamic so the most productive
information is received. One SME in health equity for behavioral health integration for
marginalized populations will be used. The SME will review the interview protocol to ensure the
questions are clearly understandable and will yield the information the researcher is seeking. The
SME is someone who has worked with the with the participant criteria in both the nonprofit and
federal setting. Once the SME provided feedback on the interview guide, revisions will be made,
thus providing reliability and credibility to the interview guide.
Procedures for Recruitment, Participation, and Data Collection
Participants for this intended study will be recruited from the general NYC population
with participant criteria set forth. The primary source of distribution for recruitment will be the
internet through the use of a recruitment flyer on the FQHCs social media platforms well as their
website, as so long as the institution approves. The second component will be for the researcher
to outreach to those who qualify for the study from the initial population list that will be
generated via the FQHC, thus making it quicker to garner willing participants. The outreach via
phone and email will be based on patients who qualify from the preliminary list. Based on the
culmination the flyer distribution and the outreach that will be conducted, it is that patients will
be interested and interviews will be conducted as interest is expressed. The intention of the
researcher is to gather 20-25 participants for this study.

82
Upon expressed interest from participants, participants will be provided the consent form
via a link that contains the study’s formal invitation and informed consent which will go over the
interview procedures; the voluntary nature of the interview; the associated risks and benefits of
being interviewed; privacy concerns; contacts and concerns and consent indication which will
serve as participants signature. Those who do not meet the criteria, or those who decline to
participate further will be sent a thank you email explaining the reason for disqualification from
the study. The next step would be for participants to complete the demographic sheet (see
Appendix C). The purpose of this collection of data is have basic data of participants as it relates
to their gender identification, age, highest level of education, occupation, income range
indication of insurance; it is relevant to participants perspectives as it relates to the information,
they will divulge from answering the interview questions.
Following completion of the demographic worksheet, participants engaged in a
semistructured, open-ended, face-to-face interview. I administered the same interview protocol
for all participants as this enhanced validity, reliability, transparency, and ethical conduct and
helped to avoid bias. At the conclusion of the interview, I followed a debriefing process, as
follows:
1. Thank participants for their engagement in this interview and answer any questions
they have.
2. State the name of the study and that of the the principal investigator (myself).
3. Reiterate the goals of the study and why this study was developed, my research
questions, and let participants know they have not been deceived in any way.

83
4. Convey the withdrawal procedures should participants decide they are no longer
interested in continuing.
5. Provide information on how the participant will be informed of the study
results.
6. Reiterate the contact information of the Walden University University
Institutional Review Board (IRB) director.
7. Provide my contact information should participants have any questions or concerns in
the future.
8. Thank participants again for their participation.
All interviews will be audio recorded via iPad and transcribed using Delve. The
completion of the interviews, along with the transcripts and the analysis, and notes from
interviews which will be kept in a research journal for which the researcher can reference during
the data analysis portion of this study. For this study, I sought IRB approval from both Walden
and the FQHC, upon that approval, the study followed the IRB guidelines and protocol for
research. An IRB-approved email was used for the purpose of this intended study, for the purpose
of contact with participants when the consent is signed and emailed back as well as the
possibility of participants having question post or pre interview. All contacts and documents
related to the participants on a password-protected computer and stored in password protected
files in a hard drive. Participants was also given an ID code in place of their name to maintain
anonymity, and all participant information will be stored for a period of no more than 5 years
following completion of the research (Walden, 2011). At any point during the process if a
participant decides they no longer want to continue, any personal data will be destroyed right
away (Walden,

84
2011).
Data Analysis Plan
Data is intended to provide contextual meaning for a study, with that in mind, the data for
this study will be transcribed and analyzed utilizing a systematic review to identify common
themes as it relates to the research question. The data analysis technique that was used was
interpretative phenomenological analysis (IPA). In qualitative research, IPA is a method used to
understand subjective experiences of individuals (J.
Smith & Osborn, 2008).
Coding
Coding procedures are a crucial step in qualitative research that involves systematically
analyzing data to identify and categorize patterns, themes, and concepts that emerge from the
data. As it relates to qualitative analysis, Saldaña (2021) defined a code as a word or short phrase
that symbolically assigns a summative, salient, essence capturing and/or evocative attribute for a
portion of language based or visual data (p. 5). The process of coding, is heuristic or a method of
discovery in which the researcher determines the code for a unit of data by careful reading and
reflection on its core meaning or content (Flick, 2013). A preliminary coding framework will be
used to guide the analysis of the data collected from participants in order to understand their
experiences (see Table 1).
Table 1
Primary code
Secondary code
Interview question
Institutional analysis and
development framework
85
Preliminary Coding
Framework
Intersectionality
Experience of oppression
1, 2, 3, 5, 6, 7
Interconnected systems
Health care systems
4, 9, 13
Institutions
Policy, law
8
The conceptual framework that grounds this study helped to develop the preliminary
coding framework. The framework establishes primary and secondary cycle codes, through the
use of academic research, government reports and other types of scholarly references to
understand the experiences of African Americans as it relates to health care delivery, health care
delivery systems and their relation to racism and its impact on care for African American patients
and lastly the influence of CIBHC.
The data analysis will be conducted as a continual iterative process that will include
multiple readings of interview transcripts, with three levels of coding that will be used to identify
themes and hypernym the themes. Each interview will be analyzed individually so that the
researcher is able to bracket out researcher biases from the findings and thoughts across all
participants. Using this particular methodology for the data analysis, bracketing will be used to
take into account the individuality of the participant interviews and exclude and minimize the
emic influence of the research during the data analysis portion, again by journaling in the
research journal as well as excluding themes that have been identified in previous participant
Governance
Government/system
4
Polycentrism
System actors
6
Health equity framework
Health equity
Health access, Health
outcomes
10, 11, 12, 13
Intersectionality-based
policy analysis
framework

86
interview (J. Smith & Osborn, 2008). Bracketing is a method used by researchers to mitigate the
potential deleterious effects of unacknowledged preconceptions related to the research (Newman
& Tufford, 2010) thus it helps the researcher to be cognizant of misconceptions that can influence
the process.
Coding Process. Consistent with IPA approach as set forth by Smith et al., (2022), the
coding process will involve rereading through the interview responses twice followed by a three-
cycle data coding process (Alase, 2017). By utilizing this particular IPA approach, the researcher
is positioned to capture and represent the core essence of the lived experiences (Alase, 2017) of
participants experiences thus keeping the focus on the phenomenon.
The first step will be preliminary reading. Each interview transcript will be given a
preliminary read after the completion of the interview. This will allow the researcher to be
familiar with the data and ensure no mishaps in the transcripts from transcription. A second
reading will be done, during this time comments and impressions will be notated in a research
journal. This will also begin the primary identification of words/phrases/ comments that stand
out. It is the intention that this initial exploratory process will not only develop questions around
the phenomenon but also bring about a level of awareness of participants experiences (Alaise,
2017).
Descriptive coding (the first cycle) will be the next step. The interview transcripts will be
read with a line-by-line analysis, as this will allow for specific words or phrases to stand out
(Saldaña, 2021). Descriptive coding will be used, since it has the ability to help a researcher
identify words or phrases based on frequency, connotation, or importance (both to the researcher

87
or participant). This cycle of coding provides authenticity to the subject matter of the study
(Alaise, 2017).
In vivo coding (the second cycle) will be the next level of coding will include a deeper
level of examination of previously underlined sections in additions to notations of frequently
repeated words and phrases in the transcripts. This level of analysis will take into consideration
the terms used by participants themselves (Saldaña, 2021) as it relates to participants experiences
and deepens my understanding of those experiences as the researcher. The goal is to develop
participant-inspired codes that are relevant to the phenomenon. Conceptual coding will be the
third cycle). In vivo coding will provide foundation for the conceptual remarks, as this level of
coding moves from remarks to interpretation. It is during this level that meaning within context
will be developed from participants experiences (Alaise, 2017). It is also during this level that
themes will begin to emerge, themes that stay true to the experiences of the participants.
Themes
Consistent with IPA, the procedures for theme development involve two levels of theme
developments, often referred to as emergent and superordinate themes (Smith et al., 2009).
Emergent themes, are insights derived from the words or documented experiences of participants.
in the case of interviews, can be recorded on the side of a transcript. Superordinate themes are
developed from emergent themes (Smith et al., 2009. Upon coding and theme development,
superordinate themes across the dataset can be developed.
Upon completion of the coding and identification of themes for each interview transcript,
the researcher will begin looking for connections between themes as well as how they align with
the research question. Utilizing strategies and steps in IPA, the emergent theme for this study will

88
be developed by focusing on chunks of transcripts and analysis of notes that will be made into
themes. From those emergent themes, connections will be made by abstracting and integrating
themes drawing out the subordinate themes from the interview data (Miller & Minton, 2016)
Specific quotes and interpretative key moments that will be formulated and identified in the data
as it relates to participants experiences.
Often times studies that utilize IPA for its analysis often illustrate descriptive and interpretive
findings (Smith et al., 2009). Studies consistent with the use of IPA can include charts, tables,
and diagrams that illustrates themes and processes (Miller & Minton, 2016. As will be the case in
this study, a table that demonstrates themes and connections that will be derived from the
interviews with the analysis of emergent and superordinate themes based on each interview. IPA
also emphasizes the importance of raw data from participants within the examples of themes
(Pietkiewicz & Smith, 2014), which will also be utilized in the table for the purpose of this
current study.
Computer-Assisted Data Analysis
In addition to manual data analysis, a computer-assisted qualitative data analysis software
will be utilized, Delve. Delve is an online/cloud based qualitative data analysis tool that codes
qualitative data, as well as analyze transcripts from interviews to find human insights (Delve,
n.d.) Since the interviews will be recorded, all of which Delve can help to do and capture all that
was said by the participants. Once transcribed, the data will be entered into Delve to code,
interpret data, find commonalities, and analyze for themes and accuracy.
Integrating the Delve analysis with hand-coded analysis has the potential to provide a
balance to this study’s data analysis. Integration also provides efficiency and automation while

89
still offering flexibility. Delve can help systematically streamline some aspects of the data as it
relates to coding and organizing data, while hand coding provides a deeper understanding of the
data and allow for more flexible and nuanced analysis. In addition to the hand coding as
discussed previously, Delve will assign codes to relevant sections of text and organizing the
codes. Alongside the analysis from Delve, a sample of data will be hand-coded for a deeper
understanding of the data and to validate the coding done using Delve, the results from Delve and
the hand-coding will be compared as well as refined where needed. The data analysis from the
Delve results will be use to do a detailed content analysis for which the hand coding can validate
and provide insight.
Issues of Trustworthiness
In qualitative research, it is the researcher’s responsibility to ensure that their study is
credible, transferable, dependable and confirmable because it not only establishes trustworthiness
(Lincoln & Guba, 1985) that has been considered and applied through the entire process of the
study, but it also ensures that the research can be replicated. Trustworthiness also has to do with
the alignment on how data is collected from participants, findings that objectively reflect data
collected from participants, how data is stored, ethical considerations, and so forth (Cypress,
2017). The researcher’s experiences and understanding of participants’ experiences will be
bracketed through the journaling method as part of the process (Tufford & Newman, 2010). All
interviews will be recorded and transcribed to guarantee accuracy and ensuring the analysis is
focusing on participants experiences. Member checking will be employed in this study to ensure
accuracy and resonance with their experiences. The process for member checking will be
provided subsequently. Another matter on concern as it relates to trustworthiness has to do with

90
the locations of interviews should it be in person. Receiving confirmation from the CMO of the
FQHC, an approved office will be available for use should a participant require an in-person
interview. This ensures confidentiality for the participant.
Credibility
Credibility, also known as "internal validity," “establishes whether the research findings
represent plausible information drawn from the participants original data and is a correct
interpretation of original views” (Korstjens & Moser, 2018, p. 121). Credibility be established
by transcribing the interview of all involved participants through a secured file. After transcribing
the interviews, researcher will engage in a process known as participant checking in which,
participants will have a copy of their interview mailed to them and asked if it captures their
perspectives in their own words or if anything is missing from the transcript (Brit et al., 2016).
Participants will have the opportunity to respond with the confirmation of the accuracy of the
transcript, a process known as interviewee transcript review (Rowlands, 2021).
Transferability
Transferability, also called "external validity," refers to "the degree to which results can
be transferred to other contexts or settings with different respondents" (Korstjens & Moser, 2018,
p.121). In this study, transferability will be achieved by ensuring that participants fully
understand the terminology used in relation to their experiences through the provision of clear
terms and descriptions (Ravitch & Carl, 2021). I will also provide a detailed account of the
study's background, methods, and participant selection, which will allow others to understand the
phenomenon under investigation and apply the findings to their own research or contexts
(Korstjens & Moser, 2018, p.122). All participants will be selected based on their alignment with

91
the study's criteria. The interview guide is being designed to elicit rich, informative responses
that are highly relevant to the research objectives. Furthermore, during the analysis, participant
behaviors and experiences will be described in detail, along with their contextual settings, to
ensure that these experiences are meaningful and transferable to other readers or researchers
(Korstjens & Moser, 2018, p.122).
Dependability
Dependability, which ensures consistency in research (Korstjens & Moser, 2018,
p. 121, p.122), will be achieved by maintaining alignment between the study's purpose, research
questions, and data collection methods, as this consistency will aid in answering the research
questions later in the study (Ravitch & Carl, 2021). Additionally, dependability will be reinforced
by having an SME review the interview questions to ensure they are relevant and aligned with
the study’s objectives.
Confirmability
Confirmability refers to "the degree to which the findings of the study can be confirmed
by other researchers for accuracy and neutrality" (Korstjens & Moser, 2018,
p.121). In this study, confirmability will be achieved by ensuring the accuracy of data analysis,
verifying that coding is done correctly, and ensuring that the identified themes are accurately
matched during the coding process. As the researcher, it is crucial that I remain aware of how my
own biases, positionality, and subjectivity may influence my interpretation of participants'
experiences. This awareness helps to secure the intersubjectivity of data interpretation and
ensures it is grounded in the data itself (Korstjens & Moser, 2018, p.122). To mitigate this, I will
carefully document any biases that emerge during the interview or transcription process.

92
Ethical Procedures
I began data collection after receiving approval from Walden University’s IRB (no. 08-
29-23-1060997) as well as from the external institutions' IRB as required. As with ethical
considerations, the confidentiality of all participants will be a priority throughout this entire
process of this study. Because of the information that participants will be sharing that will include
medical and mental health diagnosis, the confidentiality measures that will incorporate the Health
Insurance Portability and Accountability Act of 1996 (P.L. 104-191) clause that speaks to the
sharing of PHI. All documents such as the recruitment flyer, interview guide, consent form etc
will also be shared with the IRB for approval.
To consider security, contact form, informed consent, transcribed interview will be stored
a password protected file on a password protected computer. As per Walden University’s
Dissertation Guidebook, these documents will be kept for up to 5 years or until the research is
complete and once completed, will be destroyed permanently. (Walden, 2021). Participants will
be informed both verbally and in writing that their participation in this study is voluntary. At any
point during the process if they no longer want to participate their consent is automatically
withdraw and all their documents related to their participation up until that point will be
destroyed. Interviews will be done on site at the FQHC if needed in an approved office by the
external institution. As for the ramifications of confidentiality, it will be minimal as there will not
be a label or anything indicating the purpose of the what the room is for. For those participants
who choose to do it in person, they will be given a room number that only they will know, and
interviews will be scheduled in such that not participants are coming or going in or around the
same time, all of which will be explained to participants.

93
Summary
Chapter 3 focused on the important components of this qualitative explorative study; such
as research design and rationale, the role of the researcher, the methodological components of the
study, the intended methods for data analysis issues of trustworthiness and the ethical
considerations of the study. In Chapter 4, I will present the findings of the study.
Chapter 4: Results
Introduction
The purpose of this qualitative study is to understand the implementation of CIBHC as it
relates to the African Americans experience while taking into consideration health care access
and quality (SDoH), from a public policy lens. A qualitative approach was used to address the
following research question: What do African Americans think about the impact of CIBHC on
their own health outcomes and health care delivery for POC?
In this chapter, I describe the setting of the study as well as the participant demographics.
I present a synopsis of the data collection process used which includes the number of
participants, the location for data collection, and how data was collected. I will also provide the
data analysis process utilizing the IPA approach to identify the themes most common in the study.
This will be followed by a discussion of the how the trustworthiness of the study was maintained
for the collection of data as well as the data analysis. The results will then be presented, including
the emergent and superordinate themes that emerged during data analysis, supported with
excerpts from participants responses to support the themes.

94
Setting
Data for this study was collected between September 2023 and January 2024. A total of
20 participants answered 13 open-ended questions that provided insight into their lived
experiences with health care systems in the United States, and CIBHC. The participant
interviews took some time and a lot of patience to coordinate, due to the fact that participants had
obligations. In some cases, interview dates were rescheduled, changed from in-person to virtual,
room changes on part of the facility availability, and so forth. Most interviews took place in a
clinical interview room of an FQHC, and for those that were not in-person, they were facilitated
virtually.
Demographics
All participants were African American members of the African diaspora, patients of the
FQHC, had a chronic/behavioral health diagnosis, and resided within NYC.
Participants completed a demographic fact sheet prior to the interview (see Appendix C).
Participants were between the ages of 19 and 71 years old. There was an equal distribution of ten
male and female participants. The education distribution of the participants was as follows: 40%
Masters, 25% Bachelors, 20% High School Diploma, 5% of College Not Completed; 5% of
Doctorate and 5% of GED holders. The insurance distribution of the participants were as
follows: 65% Commercial, 20% Medicaid/ Managed Care, and 15% Medicare. The occupation
status among participants reflect the following: 65% employed, 20% unemployed, 10% retired,
and 5% students. Other relevant information that came up was separate from participants who
identified as African American or Black Americans, some participants identified also identified

95
Nigerian, Haitian, Grenadian-American, Afro German, and Afro Guyanese, these demographics
are displayed in Table 2.
Table 2
Participant Demographics
Participant no.
Age
(years)
Gender
Education
Insurance
Occupation
status
1
19
F
College
degree
Commercial
Student
2
21
M
HS diploma
Commercial
Employed
3
25
M
Master's
degree
Medicaid
Unemployed
4
29
M
HS diploma
Medicaid
Unemployed
5
32
F
Master's
degree
Commercial
Employed
6
33
F
Bachelor's
degree
Commercial
Employed
7
42
F
Bachelor's
degress
Commercial
Employed
8
44
M
Master's
degree
Commercial
Employed
9
49
F
Master's
degree
Commercial
Employed
10
51
M
HS diploma
Medicaid
Unemployed
11
54
F
Doctorate
Commercial
Employed
12
66
F
Master's
degree
Medicare
Employed
13
69
M
Master's
degree
Medicare
Retired
14
71
M
Bachelor's
degree
Medicare
Retired
15
39
M
Bachelor's
degree
Commercial.
Employed
16
33
F
Master's
degree
Commercial
Employed

96
17
35
M
Bachelor's
degree
Commercial
Employed
18
28
F
Master's
degree
Commercial
Employed
19
21
F
HS diploma
Medicaid
Unemployed
20
27
M
GED
Commercial
Employed
Note. F = female; M = male; HS = high school; GED = general equivalency diploma.
Data Collection
A total of 23 participants were recruited for this study using the procedures described in
Chapter 3; subsequently, one was eliminated because they did not reside in
NYC, and two others transferred out of the clinic, thus leaving a total of 20 participants. The use
of open-ended interviews for this study allowed participants to be forthcoming with their
responses and required minimal probing; it also allowed for a great amount of data to be obtained
for the purpose of this study. The duration of the interviews for this study were between 45 and
90 min. Utilizing an interview guide that I created (see Appendix B), I asked participants about
their perspectives and experiences with health care delivery related race, quality, and access, as
well as the impact CIBHC can have on health care delivery in the United States.
All interviews began with participants either receiving a copy of the consent prior to the
interview for them to sign, or for those done in person, 10–15 min were spent at the beginning to
review the consent, asking if participants had any questions/concerns, etc, followed by the
participants’ signatures. All participants then completed a demographic sheet which took about
10 to 15 min, after which rapport was developed and the interviews began. Interviews were
conducted over 6-month period from September 2023 to January 2024. All interviews were audio
recorded and transcribed using Otter.ai (Otter, 2024). During the interviews, notes were taken on
particular characteristics or things specific to the participant. Participants were in agreement that

97
they could be contacted after for further illumination if needed. Identifiable information was
removed from transcripts and for the purpose of confidentiality, participants were labeled as P1-
P20.
Unusual Circumstances During Data Collection
During the course of data collection, most participants were not familiar with culturally
behavioral integrated health care. As a result, I provided participants with the meaning of the
concept. Once it was explained participants had a better understanding of the concept and were
able to respond to the last three interview questions based on their understanding of that concept.
Data Analysis
One-on-one interviews served as the primary data collection method for this inquiry, with
all interviews being meticulously audio recorded and transcribed using the Otter.ai platform. A
transcript review process was applied in this study, after all the interviews, participants were
given a transcribed version of their interviews as asked to review them for accuracy. Corrections,
clarified meanings, and any necessary additional information participants felt necessary were
added. The updated transcripts is what were used for the analysis. These transcripts were
subsequently analyzed using the combination of hand-coded analysis and computer coding using
Delve described in Chapter 3, wherein significant phrases and statements elucidating participants'
perceptions and experiences regarding health care delivery were highlighted.
The IPA as a qualitative approach is used to investigate individual lived experiences
(Fieldsend & Smith, 2021). This particular approach allows for “microlevel exploration of
meanings that tap into the wholeness of experiences” (J. A. Smith & Fieldsend, 2021, p. 148)
complemented by the researcher's interpretations of these experiences based on participants' own

98
narratives. Leveraging Delve and Otter.ai ensured an unbiased analysis, devoid of preconceived
notions (J. Smith & Osborn, 2015).
Employing the coding process delineated by J. Smith and Osborn (2003), as referenced in
Chapter 3, aided in identifying patterns, categories, codes, and overarching themes that resonated
with participants' shared experiences. Line-by-line coding proved instrumental in developing
participant-inspired codes, subsequently facilitating the emergence of themes. These themes were
further organized into categories, underscoring commonalities across participants' experiences
and yielding superordinate themes (J. A.
Smith & Fieldsend, 2021; J. A. Smith et al., 2022; J. Smith & Osborn, 2003).
The data analysis through one-on-one interviews provided a foundation for understanding
the perspectives of participants concerning their experiences in health care. The application of
IPA was valuable in delving into the details of participants lived experiences. This qualitative
approach helped uncover explicit content as well as the implicit meanings and emotions tied to
participants narratives. The use of Delve and Otter.ai for transcription and preliminary coding
ensured high degree of accuracy and consistency in data interpretation, essential for maintaining
the integrity of quality analysis. The combination of hand-coded and computer-assisted coding
methods facilitated a comprehensive exploration of the data. By employing a line-by-line coding
technique, the study captured a wide range of expressions and sentiments that might have been
overlooked with a more generalized coding approach. The manual coding of the data allowed for
a close connection to the texture of lived experiences shared by participants. Appendix D shows
the coding analysis for the study.

99
Six superordinate themes- health care complexity and disparities, perception and
experience of health care delivery, disparities and challenges in health care access, cultural
competence and sensitivity in health care, impact of race and racism on health care, and CIBHC
–were identified as consistently resonant across all participants, reflecting their unique
perspectives on health care complexities and disparities. These themes encapsulated the
challenges and barriers to access, perceptions and experiences of health care delivery, the
imperative for cultural sensitivity and competence in health care provision, systemic biases and
inequities in health care access, the significance of cultural competence in interactions and
service delivery, and the pervasive influence of race and racism on health care encounters which
suggest that the issues in health care for African Americans are more complex and multifaceted.
Appendix E is a master table of the emergent and superordinate themes. Notably, participants
from diverse backgrounds shared these commonalities, underscoring the universality of these
experiences. Ultimately, the findings underscored the crucial role of CIBHC in mitigating stigma
and enhancing health outcomes within marginalized communities.
A member checking process was also applied in presenting the final superordinate themes
that the analysis revealed, to ensure that participants intended meanings aligned with how the
data was interpretated. A summary of the six themes was prepares, in common jargon that would
be for all to read and comprehend. A feedback process was facilitated either through Team or on
the phone individually. The feedback remained positive throughout with all participants
confirming, as participants felt that the themes truly defined their interpretations of their
perspectives in health care. No changes were needed as a result. The analysis did not have any
discrepant cases.

100
Evidence of Trustworthiness
Credibility
In qualitative research, credibility serves as a cornerstone, ensuring the authenticity and
validity of the study. The adoption of the IPA approach underscores a commitment to unraveling
the intricacies of lived experiences, a hallmark of qualitative inquiry (Bloomberg & Volpe, 2012,
p. 3). Credibility is further buttressed by the meticulous alignment between participants'
perspectives and the researcher's portrayal, as advocated by scholars (Patton, 2015; J. A. Smith et
al., 2022).
Throughout this study, participants' narratives were meticulously documented in their
own words, devoid of leading questions or imposed opinions, thereby preserving the integrity of
their accounts (Patton, 2015; J. A. Smith et al., 2022). The utilization of oneon-one interviews as
the primary data collection method facilitated the elicitation of nuanced insights, while the
integration of audio recording and transcription through Otter.ai ensured transparency in data
capture and analysis, allowing for cross-referencing between transcribed interviews and audio
files to maintain accuracy.
The analysis phase, the preliminary coding facilitated in Delve, epitomized transparency
and rigor. Key phrases and statements were methodically highlighted, facilitating traceability and
verification of interpretations. Drawing upon a coding process delineated by J. Smith and Osborn
(2003), themes, patterns, and categories were meticulously extracted from participant interview
transcripts (Saldaña, 2016; J. A. Smith et al., 2022), enhancing the reliability of the analysis. The
emergence of consistent themes across all participants further reinforces the credibility of the
findings, underscoring the robustness of the research process. By adhering to established

101
methodological principles and ensuring transparency at each stage of the research journey, this
study upholds the tenets of credibility in qualitative inquiry.
Transferability
In qualitative research, transferability denotes the extent to which the results of a study
can be generalized or applied to other contexts or communities and settings (Bloomberg & Volpe,
2012, ). This involves demonstrating that the research methods and results are robust enough
across different environments or populations to provide useful insights or to guide decision-
making in those other contexts. The research meticulously delineated the participants' profiles,
their experiential narratives, and the contextual milieu within which the investigation transpired,
affording readers the opportunity to discern the potential relevance of the findings across akin
contexts and populations. Employing the IPA methodology facilitates a profound exploration of
participants' lived realities. This approach, adept at capturing the intricacies and nuances inherent
in these experiences, furnishes insights that may reverberate with individuals confronting akin
challenges in varied settings (Pietkiewicz & Smith, 2014; J. Smith & Osborn, 2008).
To ensure a comprehensive representation, the participant sample encompasses
individuals from diverse backgrounds within the African Diaspora, exhibiting a range of
demographic characteristics as stipulated by the inclusion/exclusion criteria. Such deliberate
diversification augments the potential transferability of the findings to a broader array of
populations. The discernment of coherent themes and patterns across all participants intimates
that the implications of the findings transcend the confines of the specific individuals
interviewed. These overarching themes likely encapsulate broader phenomena or experiences
shared by individuals contending with analogous circumstances (Alase, 2017)

102
Moreover, the transparent explication of the data collection and analysis methodologies
empowers readers to evaluate the veracity of the findings and contemplate their applicability
within their own spheres of inquiry. Such transparency underpins the integrity of the study and
fortifies the foundation upon which readers may gauge the transferability of the insights
proffered. In essence, through meticulous delineation, rigorous methodological adherence, and
transparent reporting, this study endeavors to facilitate the transferability of its findings to
diverse contexts and populations, thereby enriching the discourse within the broader scholarly
landscape (Bloomberg & Volpe,
2012).
Dependability
In qualitative research, dependability involves the transparency of data collection
methods and the reliability of interpretations, ensuring that the study's findings remain consistent
and trustworthy (Bloomberg & Volpe, 2012). In this study, the use of IPA plays a crucial role in
enhancing dependability, as it promotes a systematic and structured approach to data analysis,
thereby reinforcing the consistency of the findings (J. Smith &
Osborn, 2008).
Initial impressions gleaned from participants' responses were meticulously documented in
a journal, exemplifying the researcher's commitment to transparency and methodological rigor.
The journaling served as a log of activities during the data collection and analysis phase but in
addition where methodological decions, the rational of these decions and reflections of the data’s
emerging interpretations (Ortipp, 2008). Detailed documentation such as the one used in
journaling enhances transparency of research thus helping with the validation for the study. The
comprehensive elucidation of data collection procedures affords readers the opportunity for

103
meticulous scrutiny and facilitates replication of the study's methodology (J. A. Smith et al.,
2022). Furthermore, the integration of audio recording and transcription during interviews,
coupled with the strategic highlighting of key phrases and statements, engenders an audit trail of
the research process. This audit trail not only ensures transparency but also enables subsequent
researchers to traverse the decision-making trajectory and verify the accuracy of interpretations
(J. Smith & Osborn, 2004).
The discernment of consistent themes and patterns resonating across all participants
serves as a testament to the study’s dependability. Such consistency underscores the robustness of
the findings, signifying that they are not contingent upon chance occurrences or individual
idiosyncrasies but rather encapsulate broader phenomena or shared experiences among the
participants (Alase, 2017). By adhering to rigorous methodological practices, transparent
reporting, and evidencing consistent findings, this study endeavors to fortify the dependability of
its outcomes, thereby enriching the scholarly discourse within the field (Bloomberg & Volpe,
2012).
Confirmability
In qualitative research, confirmability is the objectivity of the data and interpretations
based on participants perspectives rather than the biases of preconceptions of the researchers
(Guba & Lincoln, 1989). The study emphasized capturing participants' perspectives and
experiences in their own words without imposing leading questions or preconceived notions
(Patton, 2002). The participant-centric approach used in this study minimizes the influence of the
researcher's biases on the data (Shenton, 2004).

104
The integration of audio recording and transcription during interviews, complemented by
the meticulous highlighting of key phrases and statements, engenders a milieu of transparency
within the data collection and analysis process (Creswell, 2014). This transparency affords
readers the opportunity to trace the trajectory of the researcher's decision-making process,
thereby fortifying the confirmability of the data and interpretations (Morrow, 2005). Moreover,
the candid acknowledgment of the interpretations of participants' experiences, predicated upon
their narratives, evinces reflexivity (Finlay, 2002). Through this act of transparency, the
researcher extends an invitation for scrutiny of their interpretations, thereby fostering an
environment conducive to confirmability in the data analysis Lincoln & Guba, 1985). The
identification of consistent themes and patterns resonating across all participants stands as a
testament to the research's dedication to grounding interpretations in the data. Such consistency
serves to bolster the confirmability of the interpretations, underscoring their fidelity to the
perspectives articulated by the participants.
Results
The results of the data analysis, which was conducted using the IPA, revealed the
organization around six overaching themes that ermeged from the coding process. Six
overarching themes that provided significant insights into their health care experiences and
perspectives. These themes are (a) health care complexity and disparities, (b) perception and
experience of health care delivery, (c) disparities and challenges in health care access, (d) cultural
competence and sensitivity in health care, (e) understanding the impact of race and racism on
health care, and (f) CIBHC.

105
Coding Process
The preliminary coding framework that was developed for this study was grounded in
important theorectical concepts such as health care complexity, systemic bias and cultural
competence. The framework served as a guide for the intial coding process and allowed for a
structured approach to analyzing the data. During the coding process, the expected primary codes
such as “systemic barriers”, “disparities, and “cultural” sensitivity” did emerge promimently.
However, the iterative and interpretive aspect of the IPA allowed for additional nuanced codes
like “rushed interactions” and “trust building” which weren’t anticipated, but it was crucial in
undertsianding the lived experienced of participants.
To derive these themes, a rigourous process was utilized, which involved three rounds of
coding: descriptive, in vivo, and conceptual. This systemic approach allowed for the
identification and categorization of patterms, themes, and concepts from the data.
The themes that emerged developed from a set of codes that were consistent across participant
interviews. In total 19 codes were identified, which were categorized under the major themes.
The aggregate frequencies of these codes are summariezed in Table 3, indicating the prevalence
of each code in the data set.
Table 3
Frequency and Percentage of Codes
Code
f
%
Systemic barriers
45
15
Disparities
38
12.7
Governance structures
20
6.7
Unequal resource Distribution
30
10
Systemic biases
40
13.3
Discomfort
25
8.3

106
Dissatisfaction
18
6
Rushed interactions
15
5
Insensitivity
28
9.3
Access disparities
35
11.7
Socioeconomic barriers
22
7.3
Cultural sensitivity
32
10.7
Stereotypes
25
8.3
Need for training
29
9.7
Race
50
16.7
Racism
48
16
Discrimination
40
13.3
Behavioral health integration
35
11.7
Trust building
25
8.3
Relationship Between Codes and Themes
Each theme is grounded in specific codes that were consistently observed across
particiant interviews, highliting the prevelance and significance of these issues within the context
of African American experiences in health care.
Theme 1: Health Care Complexity and Disparities
This theme emerged from a combination of codes that highlighted systemic issues and
barriers within the health care system in the United States. The following codes contributed most
significantly to this theme:
• Systemtic Barriers ( 45 mentions, 15%): Highlighted the structural challenges faced
by African Americans in accessing quality care.
• Diaparities ( 38 mentions, 12.7%): Focused on the unequal treatement and outcomes
fro African Americans withinthe health care system.

107
• Governance Structures ( 20 mentions, 6.7%): Reflected participants concerns about
policies and regulations that perpetuate health care inequalities.
• Unequal Resource Distribution ( 30 mentions, 10%): Addressed the imbalance in
health care resources and facilites across different communites.
Theme 2: Perceptions and Experiences of Health Care Delievery
Though varied, participants experiences and interactions with health care providers were
captured through several codes:
• Discomfort (25 mentions 8.3%): Decribed feelings of unease during health care
encounters, often linked to lack of emphathy or understanding from providers.
• Dissatisfaction (18 mentions, 6%) Expressed participants overall dissaitifaction with
quality of care received.
• Rushed (15 mentions, 5%); Pointed to the hurried nature of appointments, which left
particiapnts feeling unhead and unvalued.
• Insensitivty (28 mentions, 9.3%): Highlighted instances where particpants felt their
cultural or personal concerns were not adequaltely acknowledged.
Theme 3: Disparities and Challeneges in Health Care Access
Access to health care was a significant concern for participant, with the following codes
contributing to this theme:
• Access ( 35 mentions, 11.7%): Focused on the difficulties participants faced in
accessing health care services, often due to geographic or socioeconomic factors.
• Systemic Bias ( 40 mentions, 13.3%): Captured the persuasive influence of biases
within the health care system that hinger equitable access to health care.

108
• Socioceconoomic Barriers ( 22 Mentions, 7.3%): Addressed the financial and social
obstancles that prevent African Americans from recieveing consistent and quality
health care.
Theme 4: Cultural Competence and Sensitivty in Health Care
The need for culturally competent care was a reoccurring theme brought up, supported by
the following codes:
• Cultural Sensitivity ( 32 mentions, 10.7%): Emphasize the importance of health care
providers understanding and respecting cultural differences.
• Stereotypes ( 25 mentions, 8.3%): Highlighted the negative impact of racial
stereotypes on the quality of care provided to African American patients.
• Need for Training ( 29 mention, 9.7%): Reflected participants calls for increased
cultural competence training for health care professionals.
Theme 5: Understanding of the Impact of Race and Racism on Health Care
Race and racism were major issue sthat influences all participants health care
experiences, supported by the following codes:
• Race ( 50 mentions, 16.7%): Was the mpst frequently mentioned code, illustrating its
profoundimpact on health care experiences.
• Racism: (48 mentions, 16%): Caputured participnats’ experiences with both overt and
covert forms of racial discrimination within health care settings.
• Discrimination (40 mentions, 13.3%): Highlighted the various ways in which
participnats felt discriminated against in health care enviroments.

109
Theme 6: Culturally Integrated Bheavioral Health Care
This particular theme was built upon participants advocacy and need for ways to integrate
their cultural background, cultural competence into mental health services, supported by the
following codes:
• Behaviroal Health Integration ( 35 mentions, 11.7%): Refelected participants belief
in the importance of integrating culturally aware practices into behavioral/primary
care services.
• Trust Building ( 25 mentions, 8.3%): Emphasized the role of trust in improving health
care outcomes and enagament, particulary in mental health settings.
Summary of Code Contributions
The relationship between the codes and the themes illustrate the depth of the data as well
as the serious issues identified by the participants during this process. The codes reflected
individual experiences as but it also reveals the broader systemic challenges that must be
addressed in order to improve health care outcomes for African Americans in the United States.
This detailed mapping of codes to themes ensures findings are grounded in the data as well as
aligned with the study’s objectives. Each theme will be discussed in detail to high light the
multifaceted landscape of health care disparities faced by the African American community and
to offer a nuanced understanding of their lived experiences and perceptions concerning health
care access and quality in the United
States.

110
Themes
Theme 1: Health Care Complexity and Disparities
Participants delved into the intricacies of health care complexities and disparities,
revealing deep-rooted systemic issues perpetuating unequal access to quality care among African
Americans. Governance structures, including government policies and regulatory frameworks,
emerged as significant determinants of health care disparities. Participants highlighted the impact
of systemic biases and institutional practices in exacerbating disparities in health care access,
treatment, and outcomes. Moreover, the unequal distribution of resources and health care facilities
across communities further underscored the systemic nature of health care inequities. Examples
of statements from participants that emphasize the need for systemic change to address various
disparities:
The theme is prominently highlighted throughout participants' experiences and
observations. Participant 4 emphasized the critical need for systemic change within the U.S.
health care system, particularly stressing the importance of building trust with the African
American population, especially African American males. Trust-building is essential to address
the existing complexities and disparities effectively. Participant 6 also acknowledged that while
there have been strides towards improvement, persistent disparities remain a significant
challenge. This participant called for greater equity and access to quality care, underscoring that
the journey towards equitable health care is far from complete.
Further, Participant 7 pointed out the systemic biases that African Americans face within
the health care system. These biases contribute to unique challenges, including disparities in
treatment and systemic barriers that hinder equitable health care delivery. Echoing these

111
sentiments, Participant 14 remarked that although health care services might be generally
acceptable, the delivery is far from colorblind. The participant highlighted that biases in health
care delivery are still prevalent, often determined by the color of a patient's skin, thereby
exacerbating the disparities and complexities within the system. These insights collectively
illustrate the multifaceted nature of health care complexity and disparities faced by African
Americans, emphasizing the urgent need for systemic reforms to address these persistent issues.
Theme 2: Perceptions and Experiences of Health Care Delivery
Participants articulated a wide range of perceptions and experiences regarding health care
delivery. Their encounters across the health care system were varied but not significantly
different. Based on participant feedback, interactions with health care providers were
predominantly described as discomforting, dissatisfying, rushed, and at times, insensitive.
Several participants expressed feeling unheard or dismissed during their visits, highlighting a
need for more empathetic and patient-centered care. Quotes such as "I felt like my concerns were
brushed aside" ( Participant 12) and "There were instances of insensitivity that made me feel
uncomfortable" ( Participant 8) underscore the challenges faced within health care settings.
While a few participants mentioned positive interactions with empathetic providers, the overall
sentiment pointed towards experiences that fell short of expectations, emphasizing the need for
improvements in provider communication and sensitivity to patient needs.
Participants in the interviews underscored disparities in health care access influenced by
geographic location and socioeconomic status. Participant 16 conveyed feeling rushed, stating,
"There have been instances where concerns felt rushed or inadequately addressed." Participant 7
pointed out access disparities, noting, "Access to care can vary depending on location and

112
socioeconomic status." Participant 2 shared experiences of insensitivity and miscommunication,
stating, "I've also encountered insensitivity and miscommunication." Participant 4 emphasized
the need for equitable health care delivery, stating "delivery of health care services but not
equitable."
Theme 3: Disparities and Challenges in Health Care Access
Participants described various and intricate disparities and challenges faced by African
Americans in health care access. Participants specifically cited systemic biases, preconceived
notions and feelings of not being comfortable all of which were seen as barriers to equitable care.
Participants cited many examples of subpar care during visits with their providers which was the
foundations for addressing disparities in health care access and delivery particularly with African
Americans and more particularly African American men who also revealed specific systemic
discrimination and structural inequities.
Participants in the interviews articulated a variety of disparities and challenges faced by
African Americans in accessing health care, reflecting systemic biases and barriers to equitable
care. Participant 2 recounted experiences of insensitivity and miscommunication, while
Participant 5 emphasized the need for equitable health care delivery. Participant 10 highlighted
disparities in access to care, expressing concerns about quality and affordability “There are
disparities, and getting quality care can be tough. We need better access, affordability.”, and
Participant 15 underscored the challenges African Americans face in the health care system
“unique challenges within the health care system, ranging from disparities in treatment to
systemic biases”.

113
Additional perspectives from other participants further illustrated these issues, with Participant 4
discussing biases in health care interactions and Participant 12 reflecting on disparities in
treatment outcomes. These insights collectively highlight the complex landscape of health care
access for African Americans, emphasizing the need for systemic reforms to ensure fair,
respectful, and equitable treatment within the health care system.
Theme 4: Cultural Competence and Sensitivity in Health Care
Analysis underscored the importance of cultural competence and sensitivity in health care
delivery, advocating for a more inclusive and patient centered approach.
Intersecting identities such as race and gender emerged as a prominent factor that has shaped
health care experiences and perceptions of African Americans. Throughout, participants
continually underscored the importance of providers to acknowledge and respect cultural
diversity amongst their patients, as well as establishing trust and building rapport with their
patients. Participants also highlighted more or continuous cultural competence trainings for
health care professionals of all levels, thus bettering the patient provider dynamic which they
believed will lead to better health experiences and outcome overall.
Participants in the interviews highlighted critical aspects of cultural competence and
sensitivity within health care. Participant 7 articulated the impact of stereotypes and biases faced
as an African American and German, underscoring the necessity for health care providers to
exhibit cultural sensitivity. Participant 15 emphasized ongoing disparities in health care for
African Americans, stressing the urgency of addressing systemic biases to ensure equitable and
dignified care. Participant 17 pointed out the need for enhancing cultural competence and patient

114
engagement within health care settings, while Participant 2 advocated for increased training to
improve cultural competence among providers. These perspectives
Theme 5: Understanding of the Impact of Race and Racism on Health Care
Participants all agreed that race and racism have a significant impact on their health care
interactions, the trust and rapport that is developed with their providers, access to care and
overall health outcomes. Across all participants, experiences were similar in describing unfair
treatment, discrimination and systemic bias in the health care system, all of which participants
agreed there is an important need to address racial biases in health care and promote diversity
more in health care as a whole. Participants also emphasized the effects of racial discrimination
as it relates to the care they receive, how it effects their health outcomes and so forth-
highlighting the imperativeness in addressing structural and systemic racism to achieve health
equity.
Participants in the interviews provided poignant reflections on the impact of race and
racism on health care. Participant 6 highlighted the urgent need for greater equity in health care,
emphasizing its vital role in the U.S. health care system with room for significant improvement,
especially for African Americans. Participant 14 recounted personal experiences of unfair
treatment, noting how POC are often treated unfairly, not listened to, and subjected to
preconceived notions during health care encounters. Participant 15 underscored the persistent
challenges African Americans face within health care, including disparities in treatment and
systemic biases, advocating strongly for addressing these issues to ensure fair and dignified care
for all. Participant 11 drew attention to the stark consequences of race and racism in health care,
noting how these factors contribute to earlier mortality and increased prevalence of preventable

115
illnesses among POC in health care systems. These perspectives collectively highlight the critical
need for addressing racial disparities and fostering equitable health care practices to improve
outcomes for marginalized communities.
Theme 6: Culturally Integrated Behavioral Health Care
The analysis highlighted participants acknowledgement of the benefits of CIBHC as a
potential solution to address disparities as well as promote health equity for African Americans.
Culturally tailored interventions, were identified as ways to bridge the gap in access and quality
of care, fostering trust and improving health outcomes within the African American community
as far as the health care system goes. But with culturally integrated behavioral health care,
participants expressed mental health services that address unique needs of participants, advocacy
for this model to also to be utilized in health care delivery models for the purpose of bettering
African American outcomes as well as other marginalized groups.
Participants in the interviews highlighted the transformative potential of CIBHC in
addressing disparities and improving health care outcomes. Participant 19 underscored the
benefits, noting that culturally integrated care can break down barriers to access and quality by
recognizing and addressing cultural factors influencing mental health helpseeking behaviors.
Participant 9 emphasized its role in bridging gaps, pointing out that such care can foster trust,
reduce stigma, and provide personalized interventions that resonate with African Americans.
Participant 17 echoed these sentiments, emphasizing that culturally integrated care can lead to
improved health outcomes by addressing cultural influences on mental health and increasing
treatment engagement. Participant 5 further emphasized the importance of implementation,
suggesting that culturally competent care through integration can enhance access, reduce

116
disparities, and create a more inclusive health care environment for the African American
community. These perspectives collectively highlight the potential of CIBHC to enhance mental
health support and overall wellbeing among African Americans.
Summary
The purpose of this qualitative study was to understand the implementation of
implementation of CIBHC within the context of the experiences of African Americans, while
accounting for Social Determinants of Health (SDoH), through a public policy framework.
Specifically, the research sought to ascertain African Americans' perspectives on the impact of
CIBHC on their own health outcomes and the delivery of health care services for individuals of
color. By studying this, new insights can be gained to existing research. The impact of systemic
biases, disparities in access to care, as well as experiences of racism and the experiences of
African Americans in health care systems, the findings highlight a need for targeted interventions
that address structural inequities and promote culturally competent and equitable health for
African Americans person and their communities as this is crucial for increasing health outcomes
while caring for a historically marginalized group. In Chapter 5, I will examine study results,
identify study limitations, provide recommendations for future research, discuss the implications
for positive social change, and provide an overall conclusion for the study.
Chapter 5: Discussion, Conclusions, and Recommendations
Introduction
The purpose of this qualitative study was to understand the implementation of
CIBHC within the context of the experiences of African Americans, while accounting for Social
Determinants of Health (SDoH), through a public policy framework. Specifically, the research

117
sought to ascertain African Americans' perspectives on the impact of CIBHC on their own health
outcomes and the delivery of health care services for individuals of color. The study was
conducted to fill the gap in literature that exists in health care policy concerning CIBHC that
recognizes and addresses the specific SDoH that influence low health outcomes for African
Americans. Data analysis of the study revealed six superordinate themes:
• health care complexity and disparities (Theme 1)
• perception and experience of health care delivery (Theme 2)
• disparities and challenges in health care access (Theme 3)
• cultural competence and sensitivity in health care (Theme 4)
• understanding the impact of race and racism in health care (Theme 5)
• CIBHC (Theme 6)
The results of the study provide insights into complex dynamics between the African American
community and the health care system in the United States. From participants' experiences and
perspectives, systemic bias, disparities in health care access, encounters with racism in health
care delivery, and resulting poor health outcomes.
Interpretation of the Findings
Theme 1: Health Care Disparities and Complexities
The study illuminated persistent health care disparities within the African American
community, rooted in systematic racism and socioeconomic inequalities, a reflection of histories
long prevalent hand on the state of health care where it concerns the African American
community. Manning et al. (2023) elucidated the longstanding and deleterious effects of systemic
racism on African Americans, with profound implications for their biological and physiological

118
health outcomes. As a foundation, the narratives and experiences drawn from this study
underscored the multifaceted disparities that exists across the health care system. Participant 7 so
eloquently articulated the “Access to care varies significantly based on location and
socioeconomic status, creating seemingly insurmountable barriers.” Artiga et al. (2024) support
these finding by detailing various systemic, infrastructure and inadequate insurance coverage,
disproportionately impacts marginalized communities, exacerbating disparities. This sentiment
also supports and echo’s national findings indicating the significant obstacles African Americans
face related to economic instability and geographic disparities, contributing to overly poor health
outcomes that have unfortunately impacted the African American community.
Theme 2: Perceptions and Experiences of Health Care Delivery
Participants' perceptions of health care delivery highlight how interpersonal interactions
and cultural misunderstandings influence their experiences. Participant 12’s observation—
“There’s a clear lack of understanding of our cultural needs in health care settings, which affects
how we access and receive care”—reflects a broader issue of cultural incompetence. This aligns
with findings from the Pew Research Center (2023), which reports that a substantial proportion
of African Americans experience negative interactions in health care settings, including
insufficient respect and poor communication. Such interactions can erode trust and negatively
impact the quality of care received. These insights are consistent with other studies that
emphasize the need for improved communication and cultural sensitivity in health care delivery
(Betancourt et al., 2016).
Theme 3: Disparities and Challenges in Health Care Access
The study elucidates several critical barriers that hinder health care access for

119
African Americans, reflecting deep-rooted socioeconomic and systemic inequities. Participants
highlighted how these disparities manifest in various ways, from financial constraints to
geographic obstacles. Participant 3 observed, “Even when there is access to health care services,
the costs can be prohibitive. Many of us have to choose between paying for health care or other
necessities.” This statement underscores the financial barriers that significantly impact the ability
of African Americans to obtain necessary medical care.
Geographic disparities further compound the issue. Participant 8 noted, “In some areas,
there are few health care facilities, and those that exist are often understaffed and under-
resourced.” This quote illustrates how the lack of adequate health care infrastructure in certain
regions limits access to quality care for African American communities. Supporting these
findings, Artiga et al. (2024) report that socioeconomic status and residential segregation
contribute to disparities in health care access, highlighting that individuals in marginalized
communities often face inadequate insurance coverage and fewer health care resources.
Additionally, the Pew Research Center (2023) reveals that 63% of Black adults perceive limited
access to quality medical care due to socioeconomic and geographic factors. These barriers, as
noted by participants and corroborated by literature, emphasize the urgent need for targeted
interventions to address systemic inequities and improve health care access.
Theme 4: Cultural Competence and Sensitivity in Health Care
The study underscored the critical need for cultural competence and sensitivity in health
care delivery, as participants consistently reported that a lack of cultural understanding affects
their health care experiences. Participant 12 articulated this concern, stating, “There’s a clear lack
of understanding of our cultural needs in health care settings, which affects how we access and

120
receive care.” This quote highlights the disconnect between health care providers’ cultural
competencies and the needs of African American patients.
The Office of Minority Health (2024) supports this perspective, advocating for the
integration of cultural competence and anti-racism training into medical education. This training
is essential for enhancing providers' ability to deliver care that is both respectful and responsive
to diverse cultural backgrounds. Recent research by Sue et al. (2019) further reinforces the
importance of cultural competence, showing that improved provider sensitivity leads to better
patient-provider relationships and more effective care.
Participant 5’s comment, “We carry the weight of past discrimination in every health care
encounter, where trust is a luxury we can’t afford,” underscores how historical and ongoing
biases influence the health care experiences of African Americans. This sentiment aligns with
findings from Betancourt et al. (2016), who argue that cultural humility and sensitivity are crucial
for building trust and ensuring equitable care. Integrating these principles into health care
practices is essential for improving patient outcomes and fostering a more inclusive health care
environment.
Theme 5: Understanding of the Impact of Race and Racism in Health Care
Race and racism are pivotal factors influencing health care experiences and outcomes, as
highlighted by participants in this study. Systemic racism and racial biases significantly
contribute to disparities in care, affecting the quality and accessibility of health care services for
African Americans. Participant 4 noted, “Racial biases in health care can mean receiving less
effective treatment or being dismissed altogether. It feels like our concerns are often not taken as

121
seriously.” This quote reflects the broader issue of racial discrimination in health care, where
African American patients frequently encounter differential treatment.
The findings of this study corroborate existing literature on racial discrimination within
the health care system. Artiga et al. (2024) document that racial discrimination manifests in
various forms, including unequal treatment, lower quality of care, and limited access to health
care resources. These disparities are evident in how African Americans experience and navigate
the health care system. The study’s results underscore the critical need for anti-racist policies and
practices to combat these entrenched biases.
Further complicating this issue is the intersectionality of racism with other SDoH, such as
socioeconomic status and gender. Participant 15 remarked, “It’s not just about race;
socioeconomic factors and gender also play a role in how we experience health care. These
intersecting issues mean that some of us face multiple barriers simultaneously.” This observation
aligns with Williams and Mohammed’s (2009) research, which highlights how multiple layers of
social disadvantage compound the effects of racial discrimination on health outcomes.
In addition, systemic racism intersects with socioeconomic disparities, exacerbating
health care access and quality issues. According to a Pew Research Center (2023) report, African
Americans often face compounded challenges due to lower socioeconomic status and higher
rates of residential segregation, which further restrict access to quality health care. The report
indicates that these compounded disparities result in poorer health outcomes and decreased
health care utilization among marginalized populations. Overall, the study’s findings and
participant narratives emphasize the urgent need for targeted interventions to address systemic
racism and its impact on health care.

122
Theme 6: Culturally Integrated Behavioral Health Care
The study underscores the crucial role of CIBHC in addressing disparities and enhancing
mental health outcomes for diverse populations. Research by Ellis et al. (2022) highlights the
effectiveness of culturally tailored interventions in improving patient engagement and treatment
adherence among minority groups. This evidence is supported by participants' experiences and
insights, which emphasize the need for culturally relevant practices in both mental health and
primary care settings. Participant 9 remarked, “Culturally relevant approaches in mental health
care make a big difference. When providers understand and respect our background, we’re more
likely to engage in treatment and follow through with recommendations.” This sentiment aligns
with Ellis et al.’s (2022) findings that culturally tailored interventions can significantly enhance
patient engagement and adherence to treatment plans.
Furthermore, the integration of culturally sensitive approaches into behavioral health care
is critical for improving outcomes among African American patients. Ellis et al. (2022)
demonstrate that such practices not only address the unique cultural needs of patients but also
foster a more supportive and effective therapeutic relationship. This approach ensures that care is
responsive to the diverse needs of populations, thus reducing barriers to accessing quality mental
health services. Supporting this, Participant 14 highlighted, “When behavioral health services
incorporate our cultural values and practices, it feels like the care is more personalized and
relevant. This makes it easier for us to trust and stay committed to the treatment process.” This
observation reinforces the argument for adopting culturally integrated care models as standard
practice in behavioral health care.

123
The study’s findings advocate for the widespread implementation of CIBHC models. By
ensuring that care practices are culturally relevant and sensitive, health care systems can better
address disparities and improve mental health outcomes for African American patients. The
adoption of such models aligns with the goal of providing equitable and high-quality care,
tailored to the needs of diverse populations.
Theme Interpretation Analysis
The study's findings highlight a complex interaction of systemic, cultural, and individual
factors contributing to health care disparities among African Americans. Key themes, including
health care complexity and disparities, perceptions of care, access challenges, cultural
competence, and the influence of racism, offer a thorough understanding of the barriers and
inequities faced by this population. Addressing these issues requires interventions that promote
cultural competence, enhance provider-patient interactions, and implement anti-racist policies.
Moreover, integrating culturally responsive approaches into behavioral health care can improve
patient engagement and help reduce disparities.
Application to the Conceptual Frameworks
The guiding conceptual frameworks of this study, might also help to also explain the
findings for the study.
Institutional Analysis and Development Framework
Examining the study’s findings through the lens of Ostrom’s IAD framework offers a
robust perspective for analyzing institutional structures that shape health care delivery. Ostrom’s
framework emphasizes the role of institutional arrangements and governance in addressing
collective action problems (Ostrom, 2005). The study's findings revealed entrenched disparities

124
and systemic barriers within the health care system, as evidenced by participant narratives. For
instance, Participant 7 highlighted significant access issues, noting, “Access to care can vary
depending on location and socioeconomic status. It’s a barrier that seems insurmountable at
times.” Applying Ostrom’s framework, these findings underscore key institutional factors
contributing to disparities, such as health care policies, resource allocation, and organizational
practices (Ostrom et al.,
1994). The framework highlights the need for collective action and effective governance
mechanisms to tackle these challenges, advocating for stakeholder collaboration in enacting
policy changes and enhancing health care equity.
Health Equity Framework
Interpreting the study’s findings through the lens of ETR’s HEF reveals the complex
dynamics influencing health outcomes within the African American community. At the core of
HEF is the concept of equity, which emphasizes the importance of fair access to resources and
opportunities necessary for optimal physical, emotional, and social well-being (ETR, n.d.). The
findings highlight the impact of institutional and interpersonal biases, which contribute to
disparities in health care access and poor health outcomes for African Americans (Williams &
Mohammed, 2009). The HEF framework allows stakeholders to address systemic factors that
impede equitable access, targeting the root causes of health disparities. This framework
recognizes the importance of multiple spheres of influence, including systems of power,
relationships, and individual factors, in shaping health outcomes (Marmot, 2005). By adopting a
historical and life course perspective, stakeholders can better understand the cumulative impact

125
of systemic injustices and work towards mitigating these disparities through targeted policy
reforms and community-based initiatives.
Intersectionality-Based Policy Analysis Framework
Hankivsky’s IBPA framework provides a critical lens to understand how intersecting
social identities, such as race, gender, and socioeconomic status, shape health care experiences
and outcomes (Hankivsky, 2012). The study's findings underscore the intersectional nature of
health care disparities, wherein African Americans face compounded challenges due to the
intersecting effects of racism, sexism, and socioeconomic disadvantage (Crenshaw, 1991). For
example, Participant 5 noted, “We carry the weight of past discrimination in every health care
encounter, where trust is a luxury, we can’t afford.” By acknowledging these intersecting axes of
oppression, policymakers and stakeholders can develop targeted interventions that address the
unique needs and priorities of marginalized communities (Hankivsky, 2012). Integrating an
intersectional approach into policy analysis and development helps identify and dismantle
systemic barriers that perpetuate inequities, promoting more inclusive and equitable health care
systems (Collins, 2000). The application of Hankivsky’s IBPA framework enables stakeholders to
advance policies that prioritize intersectional equity and promote the well-being of all
individuals, regardless of their social identities.
Limitations of the Study
While this study has provided insights into African Americans' perspectives on the impact
of CIBHC on their own health outcomes and the delivery of health care services for individuals
of color, it is also essential to acknowledge its limitations. Recognizing and visibly addressing
the limitations that were present in the study is important to ensure the study’s integrity as well as

126
the validity of the findings (J. A. Smith et al., 2022). In this section, several key limitations are
discussed fundamental to the methodology, design, and implementation of the study.
The findings of this study were based on a small sample size and had a particular focus on
the African American community, thus limiting its generalizability to broader populations or
contexts. There was also a geographical restriction with participants only being from NYC. The
interpretative nature of qualitative research can introduce subjectivity and researcher bias into
data collection, analysis and interpretation (Smith, 2003). Due to the subject of the study,
participants may have been influenced to respond to interview questions a certain way, despite
there being no coercion in any way (Smith, 2003). Specifically, because this study was a
qualitative one, the nature of the study was resource intensive and time consuming, thus making
the establishing of reliability and validity a difficult one despite the use of triangulation,
reflexivity and the like. Despite the limitations, the study provides valuable insights into
participants experiences that allowed for the results of this study which contributed to a deeper
understanding of the phenomena presented initially.
Recommendations
Building upon that many insights gathered from this study, a light was shed on the many
complexities surrounding the implementation of CIBHC within the African American
community, while addressing the SDoH. The health care landscape is changing almost daily, and
with that, the grappling a newer and persistent disparities and systemic biases. Thus, it is
important to translate the findings into actionable recommendations that promote equity and
improve health outcomes for African Americans. Primed by six themes elucidated by the study,
evidence-based recommendations are aimed at policymakers, health care organizations (HCOs),

127
educators, and community stakeholders. Primed by six themes elucidated by the study, evidence-
based recommendations are aimed at policymakers, HCOs, educators, and community
stakeholders with these recommendations, stakeholders will can work with one another to
address the many multifaceted issues faced by African American in health care systems.
Policy Interventions
Policymakers should prioritize the development of and implementations of policies that
address systemic biases and structural inequities within the health care system, specifically for
POC. These policies should also include policies that reduce health care disparities, improve
access to care, promote cultural competence and sensitivity for health care actors. Policies should
be geared towards addressing SDoH that disproportionately impact African Americans and other
groups of color such as housing stability, employment opportunities, food security and so forth.
Provisions within the legislation should require all HCOs to collect and report race and
ethnicity, and language so that disparities can be identified and inform target interventions, in
alignment with the Meaniful Use Criteria for Centers for Medicare & Medicaid Services (CMS,
n.d). Policies should also include the establishment of antiracism committees within HCOs to
ensure equitable and quality care is being delivered at all times. An allocation of resources should
be made specifically to CBO’s that aim to address SDOH that impact the African American
community- long-term. This investment for these interventions can help to address root causes
thus producing positive health outcomes for African Americans. An incentive here, is CMS,
CDC, and other relevant organization are focused on addressing SDOH (CDC, 2020),
organizations will be more inclined to address these issues and improve outcomes. Lastly, as it
relates to policy interventions, policymakers should invest in marginalized communities,

128
specifically funding for the expansion of primary care, mental health and preventative health
services and recruiting and retaining from those same communities so there is more incentive for
health care professionals and they better hope for the patients they serve.
Cultural Competence Training
Cultural competence plays a crucial role in helping health care providers of all levels with
the knowledge, skills and attitudes needed to deliver culturally responsive care patient
populations, including African Americans. Medical education curricula, including both
undergraduate and continuing education, are essential in fostering cultural competence among
health care practitioners. Notably, programs such as the CrossCultural Care Training program at
Harvard Medical School which integrates cultural competence education into their curricula
(Betancourt et al., 2005).
Training should also incorporate hands on experiences such as cultural immersion,
community-based learning, and stimulated patient encounters. Hands on training will allow
health care providers to gain first hand insights into various cultural beliefs and practices thus
developing empathy and experiences of marginalized communities. An example of this is the
Community Health Immersion program at the University of California, San Francisco that allows
medical students to engage directly with underserved communities to enhance cultural
understandings and patient care skills (U. of California, San Francisco, n.d). HCO leaders should
employ ongoing assessment and evaluations to check the effectiveness of the cultural
competence training initiatives. This also includes feedback from all stakeholders to have a full
worldwide view of how things are going. HCO leaders should include cultural competence

129
initiatives as part of the organizational quality improvement initiatives to ensure alignment with
quality and equity goals.
Community Engagement and Empowerment
Community engagement and empowerment is another important component. Firstly,
HCOs, CBOs, faith-based organizations, and other relevant entities are encouraged to collaborate
and establish partnerships aimed at addressing disparities and promoting health equity in African
American communities. The partnerships have to be rooted in respect, empowerment trust and
decision making while focusing on long term relationships with each other. Program building
with federal organizations the National Institute on Minority Health & Health Disparities who
focus on empowering individuals to make informed decisions about their health and navigate
systems effectively (NIMH, n.d.).
The conduction of a community needs assessment is also necessary to identify unique
needs and priorities of African American communities. Thus, allowing HCOs to tailor their
interventions to address specific needs. Capacity building with African American communities is
also an important aspect, it will allow members of the community to actively participate in
decision making related to their health. Capacity building includes empowering individuals to
advocate for their health care needs, in which HCO’s can help foster ownership and self-
determination within African American communities. HCOs also have a responsibility to
prioritize health literacy and education initiatives to increase awareness, knowledge
understanding of health topics in a way in which the African American community will
understand thus allowing individuals to make well informed decisions about their health and
advocate for their health needs. And lastly, HCOs have the responsibility of the engagement of

130
policy advocacy and systems changes by mobilizing community members to advocate for policy
change.
Health equity zones represent a strategic practice adopted in several states, integrating
comprehensive approaches to address Social Determinants of Health (SDOH) through
community-driven strategies within designated zones (Rudolph et al., 2015). Currently, health
equity zones initiatives have been implemented primarily in Rhode Island, Massachusetts,
California, Maryland, and New York. However, expanding these initiatives to a national and
federal level could significantly enhance their effectiveness in addressing systemic health
disparities. Therefore, as a sub-recommendation, advocating for the implementation of Health
Equity Zones at the federal and national levels is proposed to comprehensively address SDOH
across broader geographic and demographic contexts.
Expansion of Culturally Integrated Behavioral Health Care
CIBHC offers a promising approach to addressing health disparities and promoting health
equity for African Americans. HCOs should prioritize true integration of behavioral health
services into primary care services, where individuals can seek both physical and mental health
concerns. Embedding behavioral health providers within the primary care team providers, HCOs
can ensure quality, coordinated mental health services for African American patients. Within this,
interventions should be tailored to the unique needs, preferences and cultural backgrounds of
patients, including culturally relevant treatment modalities, therapeutic techniques, and
communication styles into best clinical practices. Intervention should address SDoH that impact
mental health outcomes within the African American community as well such as racism,
discrimination, poverty, social isolation. In partnership with CBOs and other stakeholders, they

131
will assist to deliver services by influencing community resources and infrastructure thus
enhancing reach and impact of interventions. Another important aspect to CIBHC is the peer
support and the advocacy, which involved peer led support groups, mentorship program,
advocacy training/programs that promote self-advocacy, all of which can be facilitated by HCOs
to promote healing and recovery. It will also be important for CBOs and HCOs to provide
ongoing training and education to effectively engage with African American patients and address
their unique needs.
Research and Evaluation
In order to understand, identify and inform on evidenced based, best practices that drive
continuous improvement in health care delivery, research and evaluation plays a crucial role in
this as well. Longitudinal studies should be conducted to examine the longterm effects of CIBHC
interventions on integrated care outcomes, utilization and quality of life among African
Americans. Mixed methods research will also capture complexity and diversity of experiences of
African Americans with applied CIBHC intervention. The long-term research should be a
community engaged approach that involves African American communities. The research
findings should be shared with policymakers, community leaders, HCOs, CBOs, and the general
public. The evaluation effort should also be from an equity lens considering the foundation of
this work.
In conclusion, the recommendations outlined are essential steps towards addressing the
challenges faced by African Americans within the health care system and promoting health
equity. By addressing systemic biases, improving cultural competence, engaging communities,
expanding CIBHC and prioritizing reach and evaluation, stakeholder will be able to work

132
collaboratively work to create sustainable change, ultimately improving the health outcomes and
promoting well-being of African American individuals and their communities.
Implications
Positive Social Change Implications
This study illuminates significant health care disparities affecting the African American
community, underscoring an urgent imperative for social change to rectify systemic inequities.
By pinpointing contributing factors such as systemic bias, structural barriers, and historical
injustices, the study advocates for transformative policies aimed directly at promoting health
equity. These policies should prioritize CIBHC, address SDoH, and enhance cultural competence
among health care providers, support staff, and patients. Furthermore, community engagement
and empowerment are crucial, emphasizing collaborative efforts among stakeholders to develop
tailored interventions that meet the specific needs of local communities. This comprehensive
approach seeks to foster sustainable improvements in health outcomes and equity across
marginalized populations.
Methodological, Theoretical, and Empirical Implications
From a methodological perspective, the study emphasizes the value of qualitative
research in capturing nuanced experiences and perspectives of marginalized communities. The
study provided insights into the lived experiences of African Americans within the health care
system. This approach allowed for a deeper understanding of the complex dynamics that shape
health care outcomes, complementing quantitative studies and providing a more holistic view of
health care disparities.

133
Theoretical implications of the study lie in its application of frameworks such as Ostrom's
IAD framework, ETR's HEF, and Hankivsky’s IBPA framework. These frameworks provide
conceptual lenses through which to interpret the study's findings, offering theoretical frameworks
for understanding the intersection of race, health care, and SDoH. Empirically, the study
contributes to the growing body of literature on CIBHC and its impact on health outcomes for
African Americans. By synthesizing existing research and offering evidence-based
recommendations, the study provides valuable insights for researchers, policymakers, and
practitioners working to address health care disparities.
Recommendations for Practice
This study proposes several evidence-based recommendations for practice aimed at
enhancing health care delivery and advancing health equity. Key recommendations include
implementing policy interventions to address systemic biases and structural inequities within the
health care system, such as the systematic collection of race and ethnicity data to identify
disparities and the establishment of anti-racism committees within HCOs. Furthermore, there is a
call for substantial investments in cultural competence training for health care providers to ensure
the delivery of culturally responsive care for African American patients.
Emphasizing community engagement and empowerment, the study advocates for
collaborative partnerships among HCOs, CBOs, and faith-based entities to mitigate disparities
and promote health literacy initiatives. Additionally, expanding CIBHC services is recommended
to better align with the needs of African American patients. Lastly, the study underscores the
importance of ongoing research and evaluation to inform evidence-based interventions and foster
continuous improvement in health care delivery. These recommendations collectively offer

134
actionable strategies for stakeholders to pursue health equity and enhance health outcomes within
African American communities.
Conclusion
This study was designed to ascertain African Americans' perspectives on the impact of
CIBHC on their own health outcomes and the delivery of health care services. Study findings
underscore the pervasive impact of systemic bias, structural barriers, and historical injustices on
health care outcomes, highlighting the urgent need for transformative interventions and fostering
cultural competence and promoting health equity. By applying conceptual frameworks such as
Ostrom's IAD framework, ETR's HEF, and Hankivsky's IBPA framework, the study has provided
theoretical lenses through which to interpret its findings, contributing to a deeper understanding
of the complex interplay between race, health care, and SDoH. Moreover, the study offers
evidence-based recommendations for practice, including policy interventions, cultural
competence training, community engagement, and the expansion of CIBHC services, aimed at
addressing health care disparities and promoting equitable access to care for African Americans.
Overall, this study underscores the imperative for collaborative efforts among stakeholders to
enact meaningful change and improve health outcomes for
African American individuals and communities.

135
References
Adekson, M. O. (2021). African Americans and mental health: Practical and strategic solutions
to barriers, needs, and challenges. Springer Cham.
https://doi.org/10.1007/978-3-030-77131-7
Advancing Integrated Mental Health Solutions Center. (n.d.). About collaborative care.
University of Washington, Department of Psychiatry and Behavioral Services.
https://aims.uw.edu/collaborative-care
Academy for Integrating Behavioral Health and Primary Care. (n.d.). What is integrated
behavioral health care (IBHC)? Agency for Healthcare Research and Quality, U.S.
Department of Health and Human Services.
https://integrationacademy.ahrq.gov/products/behavioral-health-measuresatlas/what-is-
ibhc
Agency for Toxic Substances and Disease Registry. (2015, June 25). Chapter 1: Models and
frameworks. U.S. Department of Health and Human
Services. https://www.atsdr.cdc.gov/communityengagement/pce_models.html
Alase, A. (2017). The interpretative phenomenological analysis (IPA): A guide to a good
qualitative research approach. International Journal of Education and Literacy
Studies, 5(2), 9–19. https://doi.org/10.7575/aiac.ijels.v.5n.2p.9
Alzheimer's Association. (2023). 2023 Alzheimer's disease facts and figures. Alzheimer's
& Dementia, 19(4), 1598–1695. https://doi.org/10.1002/alz.13016
Anderson, L. M., Scrimshaw, S. C., Fullilove, M. T., Fielding, J. E., Normand, J., & Task
Force on Community Preventive Services (2003). Culturally competent healthcare
systems. A systematic review. American Journal of Preventive Medicine, 24(3,

136
Suppl.), 68–79. https://doi.org/10.1016/s0749-3797(02)00657-8
Artiga, S., Hill, L., & Preciado, M. (2024, February 22). How present-day health disparities for
Black people are linked to past policies and events. KFF. https://www.kff.org/racial-
equity-and-health-policy/issue-brief/howpresent-day-health-disparities-for-black-
people-are-linked-to-past-policies-andevents/
Bassett, M. T., & Graves, J. D. (2018). Uprooting institutionalized racism as public health
practice. American Journal of Public Health, 108(4), 457–
458. https://doi.org/10.2105/ajph.2018.304314
Betancourt, J. R., Green, A. R., & Carrillo, J. E. (2003). Cultural competence in health care:
Emerging frameworks and practical approaches. Public Health
Reports, 118(4), 293–302. https://doi.org/10.1016/S0033-3549(04)50253-4
Betancourt, J. R., Green, A. R., & Carrillo, J. E. (2002, October). Cultural competence in health
care: Emerging frameworks and practical approaches (Publication No.
576). The Commonwealth Fund.
https://www.commonwealthfund.org/sites/default/files/documents/___media_files
_publications_fund_report_2002_oct_cultural_competence_in_health_care__eme
rging_frameworks_and_practical_approaches_betancourt_culturalcompetence_57
6_pdf.pdf
Blackmore, M. A., Patel, U. B., Stein, D., Carleton, K. E., Ricketts, S. M., Ansari, A. M.,
& Chung, H. (2022). Collaborative care for low-income patients from racial-
ethnic minority groups in primary care: Engagement and clinical outcomes.
Psychiatric Services, 73(8), 842–
848. https://doi.org/10.1176/appi.ps.202000924

137
Bleich, S. N., Findling, M. G., Casey, L. S., Blendon, R. J., Benson, J. M., Steel
Fisher, G. K., Sayed, J. M., & Miller, C. (2019). Discrimination in the United
States: Experiences of Black Americans. Health Services Research, 54(Suppl. 2),
1399–1408. https://doi.org/10.1111/1475-6773.13220
Bloomberg, L. D., & Volpe, M. (2018). Completing your qualitative dissertation: A road map
from beginning to end. SAGE Publications.
https://doi.org/10.4135/9781452226613
Blue Cross Blue Shield Association. (2022, May 31). Racial disparities in diagnosis and
treatment of major depression (Publication No. 21-395-V05).
https://www.bcbs.com/dA/e09e583ba5/fileAsset/HOA-Racial-Disparities-
Depression_2023.pdf
Boateng, G. O., Neilands, T. B., Frongillo, E. A., Melgar-Quiñonez, H. R., & Young, S. L.
(2018). Best practices for developing and validating scales for health, social, and
behavioral research: A primer. Frontiers in Public
Health, 6. https://doi.org/10.3389/fpubh.2018.00149
Braveman, P., & Gottlieb, L. (2014). The social determinants of health: It's time to consider the
causes of the causes. Public Health Reports, 129(1), 19-31.
https://doi.org/10.1177/00333549141291s206
Brisboe, M. C., Morris, M., & De Loë, R. (2018). Augmenting the IAD framework to reveal
power in collaborative governance – An illustrative application to resource industry dominated
processes. World Development, 120, 159-
168. https://doi.org/10.1016/j.worlddev.2018.02.017
138
Burkett, C. A. (2017). Obstructed use: Reconceptualizing the mental health (helpseeking)
experiences of Black Americans. Journal of Black Psychology, 43(8),
813–835. https://doi-org.ezp.waldenulibrary.org/10.1177/0095798417691381
Capps, L. (2003). Unequal treatment: Confronting racial and ethnic disparities in healthcare.
JAMA: The Journal of the American Medical Association, 290(18),
2487-a-2488. https://doi.org/10.1001/jama.290.18.2487-b
Center on Budget and Policy Priorities. (2020, April 14). Policy basics: Introduction to medicaid.
https://www.cbpp.org/research/health/introduction-to-medicaid
Centers for Medicare & Medicaid Services. (2023). The Mental Health Parity and
Addiction Equity Act (MHPAEA). Centers for Medicare & Medicaid Services |
CMS. https://www.cms.gov/CCIIO/Programs-and-Initiatives/Other-Insurance-
Protections/mhpaea_factsheet
Centers for Medicare & Medicaid Services. (2024). Specialty care. Centers for Medicare &
Medicaid Services | CMS.
https://www.cms.gov/priorities/innovation/keyconcepts/specialty-care
Centers for Medicare & Medicaid Services. (2021). Opportunities in Medicaid and CHIP to
Address Social Determinants of Health (SDOH) (SHO# 21-
001). https://www.medicaid.gov/federal-policyguidance/downloads/sho21001.pdf
Cole, D. H., Epstein, G., & McGinnis, M. D. (2019). The utility of combining the IAD and SES
frameworks. International Journal of the Commons, 13(1),
244. https://doi.org/10.18352/ijc.864
139
Cole, M., Jolliffe, M., So-Armah, C., & Gottlieb, B. (2022). Power and participation: How
community health centers address the determinants of the social determinants of health.
NEJM Catalyst, 3(1). https://doi.org/10.1056/cat.21.0303
College of Physicians of Philadelphia. (2022). Medicinal practices of enslaved peoples.
The College of Physicians of
Philadelphia. https://collegeofphysicians.org/programs/education-blog/medicinalpractices-
enslaved-peoples
Collins, P. H. (2000). Black Feminist Thought: Knowledge, Consciousness, and the
Politics of Empowerment. Routledge.
Community Based Organizations, 20 USC § 7801(6) (2011).
https://www.govinfo.gov/content/pkg/USCODE-2011-title20/html/USCODE-
2011-title20-chap70-subchapIX-partA-sec7801.htm
Cook, J. A., Morrow, M., & Battersby, L. (2017). Intersectional policy analysis of selfdirected
mental health care in Canada. Psychiatric Rehabilitation Journal, 40(2),
244-251. https://doi.org/10.1037/prj0000266
Coughlin, S. S., Mann, P., Vernon, M., Young, L., Ayyala, D., Sams, R., &
Hatzigeorgiou, C. (2019). A logic framework for evaluating social determinants of health
interventions in primary care. Journal of Hospital Management and
Health Policy, 3(23). https://doi.org/10.21037/jhmhp.2019.09.03
Crenshaw, K. (1991). Mapping the Margins: Intersectionality, Identity Politics, and
Violence against Women of Color. Stanford Law Review, 43(6), 1241-1299.

140
Creswell, J. W. (2014). Research design: Qualitative, quantitative, and mixed methods
approaches. SAGE Publications.
Creswell, J. W., & Plano Clark, V. L. (2018). Designing and conducting mixed methods research
(3rd ed.). SAGE Publications
Cypress, B. S. (2017). Rigor or reliability and validity in qualitative research. Dimensions of
Critical Care Nursing, 36(4), 253-
263. https://doi.org/10.1097/dcc.0000000000000253
Damian, A. J., & Gallo, J. J. (2018). Models of care for populations with chronic conditions and
mental/behavioral health comorbidity. International Review of
Psychiatry, 30(6), 157-169. https://doi.org/10.1080/09540261.2019.1568233
Darity, W. S., & Mullen, K. (2020, June 15). Black reparations and the racial wealth gap.
Brookings. https://www.brookings.edu/blog/up-front/2020/06/15/blackreparations-and-
the-racial-wealth-gap/
Dawes, D. E. (2018). The future of health equity in America: Addressing the legal and political
determinants of health. Journal of Law, Medicine & Ethics, 46(4), 838-
840. https://doi.org/10.1177/1073110518821976
Dehon, E., Weiss, N., Jones, J., Faulconer, W., Hinton, E., & Sterling, S. (2017). A systematic
review of the impact of physician implicit racial bias on clinical decision making.
Academic Emergency Medicine, 24(8), 895-
904. https://doi.org/10.1111/acem.13214
Dhakal, K. (2022). NVivo. Journal of the Medical Library Association, 110(2), 270-272.
http://dx.doi.org/10.5195/jmla.2022.1271

141
Drake, P., & Rodowitz, R. (2022, April 21). Tracking social determinants of health during the
COVID-19 pandemic.
Druss, B. G., Von Esenwein, S. A., Glick, G. E., Deubler, E., Lally, C., Ward, M. C., & Rask, K.
J. (2017). Randomized trial of an integrated behavioral health home: The health outcomes
management and evaluation (HOME) study. American Journal of Psychiatry, 174(3),
246-255. https://doi.org/10.1176/appi.ajp.2016.16050507
Druss, B. G., & Goldman, H. H. (2018). Integrating health and mental health services: A past and
future history. American Journal of Psychiatry, 175(12), 1199-
1204. https://doi.org/10.1176/appi.ajp.2018.18020169
Economic Opportunity Act of 1964, 88 U.S.C. § 452 et seq. (1964)
Ellis, D. M., Draheim, A. A., & Anderson, P. L. (2022). Culturally adapted digital mental health
interventions for ethnic/racial minorities: A systematic review and metaanalysis. Journal
of Consulting and Clinical Psychology, 90(10), 717–733.
https://doi.org/10.1037/ccp0000759
Entress, R. M., & Anderson, K. M. (2020). The politics of health care: Health disparities, the
Affordable Care Act, and solutions for success. Social Work in Public
Health, 35(4), 152-162. https://doi.org/10.1080/19371918.2020.1767750
ETR. (n.d.). Health equity framework. https://www.etr.org/about-us/health-equityframework/
Finkelman, P. (2012, December 1). The monster of Monticello. The New York Times - Breaking
News, US News, World News and
Videos. https://www.nytimes.com/2012/12/01/opinion/the-real-
thomasjefferson.html?pagewanted=all

142
Finlay, L (2002). “Outing” the researcher” The provenance, the process, and practice of
reflexivity. Qualitative Health Research, 12(4), 531-545.
Flick, U. (2013). Fundamentals of Qualitative Data Analysis. In The SAGE handbook of
qualitative data analysis. SAGE.
Funk, C. (2023, March 1). 3. Black Americans’ views about health disparities, experiences with
health care. Pew Research Center Science &
Society. https://www.pewresearch.org/science/2022/04/07/black-americansviews-about-
health-disparities-experiences-with-health-care/
Garfield, R. L., Zuvekas, S. H., Lave, J. R., & Donohue, J. M. (2011). The impact of national
health care reform on adults with severe mental disorders. American
Journal of Psychiatry, 168(5), 486-
494. https://doi.org/10.1176/appi.ajp.2010.10060792
Geiger Gibson Program in Community Health. (n.d.). Timeline | community health center
chronicles. CHroniCles. Retrieved September 23, 2022, from
https://www.chcchronicles.org/histories
Hankivsky, O. (2012). Intersectionality and the Politics of Policy Analysis. Routledge.
Hankivsky, O., Grace, D., Hunting, G., Giesbrecht, M., Fridkin, A., Rudrum, S., Ferlatte, O., &
Clark, N. (2014). An intersectionality-based policy analysis framework: Critical
reflections on a methodology for advancing
equity. International Journal for Equity in
Health, 13(1). https://doi.org/10.1186/s12939-014-0119-x
Harris, A. P., & Pamukcu, A. (2020). The Civil Rights of Health: A New Approach to

143
Challenging Structural Inequality. UCLA Law Review, 67(4), 758–832.
Health Resources & Services Administration. (2022). What is a health center? Bureau of Primary
Health Care. https://bphc.hrsa.gov/about-health-center-program/whathealth-center
Heikkila, T., & Andersson, K. (2021). Policy design and the added-value of the institutional
analysis development framework. Practical Lessons from Policy
Theories, 151-172. https://doi.org/10.1332/policypress/9781447359821.003.0008
HHS historical highlights. (2021, October 4).
HHS.gov. https://www.hhs.gov/about/historical-highlights/index.html
Hodge, C., Hare, B., Luhby, T., Goodstein, E., Krishnakumar, P., Lancy, N., Lyles, T., Roberts,
A., & Alwahab, C. (2021). Burned from the land: How 60 years of racial violence shaped
America.
CNN. https://www.cnn.com/interactive/2021/05/us/whitewashing-of-americaracism/
Hogan, V., Rowley, D. L., White, S. B., & Faustin, Y. (2018). Dimensionality and R4P:
A health equity framework for research planning and evaluation in African
American populations. Maternal and Child Health Journal, 22(2), 147-
153. https://doi.org/10.1007/s10995-017-2411-z
Holden, K. B., McGregor, B. S., Blanks, S. H., & Mahaffey, C. (2012). Psychosocial, socio-
cultural, and environmental influences on mental health help-seeking among African-American
men. Journal of Men's Health, 9(2), 63-
69. https://doi.org/10.1016/j.jomh.2012.03.002
Janz, N. K., & Becker, M. H. (1984). The health belief model: A decade later. Health
Education Quarterly, 11(1), 1-47. https://doi.org/10.1177/109019818401100101

144
Kaiser Family Foundation (KFF). (2014). Summary of coverage provisions in the Patient
Protection and Affordable Care Act. KFF. https://www.kff.org/health-
costs/issuebrief/summary-of-coverage-provisions-in-the-patient
Kaiser Family Foundation (KFF). (2020). Employer-sponsored coverage rates for the Nonelderly
by race/Ethnicity. KFF. https://www.kff.org/other/stateindicator/nonelderly-employer-
coverage-rate-
byraceethnicity/?currentTimeframe=0&sortModel=%7B%22colId%22:%22Locatio
n%22,%22sort%22:%22asc%22%7D
Kaiser Family Foundation (KFF). (2021). Medicaid expansion in 2021 the impact on uninsured
rates and the implications for policy. KFF.
https://www.kff.org/medicaid/issue-brief/medicaid-expansion-in-2021-theimpact-on-
uninsured-rates-and-the-implications-for-policy
Kaiser Family Foundation (KFF). (2021) https://www.kff.org/coronavirus-covid19/issue-
brief/tracking-social-determinants-of-health-during-the-covid-19pandemic
Katon, W. (1995). Collaborative management to achieve treatment guidelines. Impact on
depression in primary care. JAMA: The Journal of the American Medical
Association, 273(13), 1026-1031. https://doi.org/10.1001/jama.273.13.1026
Korstjens, I., & Moser, A. (2018). Series: Practical guidance to qualitative research. Part
4: Trustworthiness and publishing. European Journal of General Practice, 24(1),
120-124
Lange, K. W. (2021). Rudolf Virchow, poverty and global health: From “politics as medicine on a
grand scale” to “health in all policies”. Global Health
145
Journal, 5(3), 149-154. https://doi.org/10.1016/j.glohj.2021.07.003
Lazo, K. (2019). Governing the health commons: An institutional analysis and development
(IAD) framework on health devolution in greater manchester [Doctoral dissertation].
https://e-space.mmu.ac.uk/id/eprint/626071
Lefkowitz, B. (2007). Community health centers: A movement and the people who made it
happen. Rutgers University Press.
Leong, D., & Roberts, E. (2013). Social Determinants of Health and the Affordable Care
Act. Rhode Island Medical Journal, 96(7), 20-
22. http://www.rimed.org/rimedicaljournal/2013/07/2013-07-20-sdh-aca.pdf
Lewis, M. E., & Myhra, L. L. (2018). Integrated care with Indigenous populations:
Considering the role of health care systems in health disparities. Journal of Health
Care for the Poor and Underserved, 29(3), 1083-
1107. https://doi.org/10.1353/hpu.2018.0081
Lincoln, Y. S., & Guba, E. G. (1985). Naturalistic inquiry. Newbury Park, CA: SAGE
Publications.
Liu, R., Shi, L., Meng, Y., He, N., Wu, J., Yan, X., & Hu, R. (2021). The institutional primary
healthcare service quality and patients’ experiences in Chinese community health centres: Results
from the Greater Bay Area study,
China. International Journal for Equity in
Health, 20(1). https://doi.org/10.1186/s12939-021-01538-8
Mac-Seing, M., Zinszer, K., Eryong, B., Ajok, E., Ferlatte, O., & Zarowsky, C. (2020). The
intersectional jeopardy of disability, gender and sexual and reproductive health:

146
Experiences and recommendations of women and men with disabilities in northern
Uganda. Sexual and Reproductive Health Matters, 28(2), 269-
283. https://doi.org/10.1080/26410397.2020.1772654
Maly, A., & Vallerand, A. H. (2018). Neighborhood, socioeconomic, and racial influence on
chronic pain. Pain Management Nursing, 19(1), 14-
22. https://doi.org/10.1016/j.pmn.2017.11.004
Maness, S. B., Merrell, L., Thompson, E. L., Griner, S. B., Kline, N., & Wheldon, C. (2020).
Social determinants of health and health disparities: COVID-19 exposures and mortality
among African American people in the United States. Public Health
Reports, 136(1), 18-22. https://doi.org/10.1177/0033354920969169
Manning, M., Byrd, D., Lucas, T., & Zahodne, L. B. (2023). Complex effects of racism and
discrimination on African Americans' health and well-being: Navigating the status quo.
Social Science & Medicine, 316,
115421. https://doi.org/10.1016/j.socscimed.2022.115421
Marmot, M. (2005). Social determinants of health inequalities. The Lancet, 365(9464),
1099-1104.
Marshall, B., Cardon, P., Poddar, A., & Fontenot, R. (2015). Does sample size matter in
qualitative research?: A review of qualitative interviews in is research. Journal of
Computer Information Systems, 54(1), 11-22.
https://doi.org/10.1080/08874417.2013.11645667
Martinez, L. S., Lundgren, L., Walter, A. W., Sousa, J., Tahoun, N., Steketee, G., Hahm, H.,
Mueser, K. T., Krull, I., Do, D. L., & Saitz, R. (2019). Behavioral health, primary care
integration, and social work’s role in improving health outcomes in communities of color:

147
A systematic review. Journal of the Society for Social Work & Research, 10(3), 441–457.
https://doiorg.ezp.waldenulibrary.org/10.1086/704070
Martínez-Mesa, J., González-Chica, D. A., Duquia, R. P., Bonamigo, R. R., & Bastos, J. L.
(2016). Sampling: how to select participants in my research study? Anais brasileiros de
dermatologia, 91(3), 326–330. https://doi.org/10.1590/abd1806-
4841.20165254
McBride, K., Carlson, M., & Everett, B. (2022). Using the intersectionality-based policy analysis
framework to evaluate a policy supporting sexual health and intimacy in long-term care,
assisted living, group homes & Supported housing. Journal of
Applied Gerontology, 0(0),
073346482210997. https://doi.org/10.1177/07334648221099728
McGinnis, M. D. (2011). An introduction to IAD and the language of the Ostrom workshop: A
simple guide to a complex framework. Policy Studies Journal, 39(1),
169-183. https://doi.org/10.1111/j.1541-0072.2010.00401.x
McGinnis, M. D. (2020). Revisiting the foundations of institutional analysis: Bounded
rationality, methodological individualism, and polycentricity. Policy Studies
Journal, 48(1), 5-24. https://doi.org/10.1111/psj.12345
McMorrow, S., Hancher-Rauch, H., Ohmit, A., & Roberson, C. (2021). Community-led mental
health promotion for people of color in the United States. Mental Health & Prevention,
22. https://doiorg.ezp.waldenulibrary.org/10.1016/j.mhp.2021.200203
Medicaid.gov. (2022, May). May 2022 Medicaid & CHIP enrollment data highlights.
148
(2022, May). . https://www.medicaid.gov/medicaid/programinformation/medicaid-and-
chip-enrollment-data/report-highlights/index.html
Meessen, B. (2020). Health system governance: Welcoming the reboot. BMJ Global
Health, 5(8), e002404. https://doi.org/10.1136/bmjgh-2020-002404
Medicaid and CHIP Payment and Access Commission.. (2016, March). Overview of
Medicaid Policy on Disproportionate Share Hospital Payments.
https://www.macpac.gov/wp-content/uploads/2016/03/Overview-of-Medicaid-
Policy-on-Disproportionate-Share-Hospital-Payments.pdf
Medicaid and CHIP Payment and Access Commission. (2022, May 3). Disproportionate share
hospital payments. https://www.macpac.gov/subtopic/disproportionateshare-hospital-
payments/
Michener, J. (2022, January 20). A racial equity framework for assessing health policy.
The Commonwealth
Fund. https://www.commonwealthfund.org/publications/issuebriefs/2022/jan/racial-
equity-framework-assessing-health-policy
Morrow, S. L. (2005). Quality and trustworthiness in qualitative research in counseling
psychology. Journal of Counseling Psychology, 52(2), 250-260.
Mosher, D. K., Hook, J. N., Captari, L. E., Davis, D. E., DeBlaere, C., & Owen, J. (2017).
Cultural humility: A therapeutic framework for engaging diverse clients. Practice
Innovations, 2(4), 221-233. https://doi.org/10.1037/pri0000055
National Association of Community Health Centers. (2022, September 1). Research fact sheets
and infographics. https://www.nachc.org/research-and-data/research-factsheets-and-
infographics/
149
National Conference of State Legislatures. (2021). US health care spending: Cost containment
overview. Legislative News, Studies and Analysis | National Conference of State
Legislatures. https://www.ncsl.org/health/us-health-carespending-cost-containment-
overview
National Institute of Mental Health. (2020). NIMH » mental illness. NIMH »
Home. https://www.nimh.nih.gov/health/statistics/mental-illness#
Navarro AM, Voetsch KP, Liburd LC, Giles HW, Collins JL. (2007). Charting the future of
community health promotion: recommendations from the National Expert Panel on
Community Health Promotion. Prev Chronic Disease 4(3), from:
http://www.cdc.gov/pcd/issues/2007/ jul/07_0013.htm
Nong, P., Raj, M., Creary, M., Kardia, S. L., & Platt, J. E. (2020). Patient-reported experiences of
discrimination in the US health care system. JAMA Network
Open, 3(12), e2029650. https://doi.org/10.1001/jamanetworkopen.2020.29650
Nowell, L. S., Norris, J. M., White, D. E., & Moules, N. J. (2017). Thematic analysis:
Striving to meet the trustworthiness criteria. International Journal of Qualitative
Methods, 16(1), 160940691773384. https://doi.org/10.1177/1609406917733847
Office of Minority Health. (2021). National Partnership for Action to End Health
Disparities. Retrieved from https://minorityhealth.hhs.gov/npa/
Office of Minority Health. (2021). National Standards for Culturally and Linguistically
Appropriate Services (CLAS) in Health and Health Care. Retrieved from
https://minorityhealth.hhs.gov/omh/browse.aspx?lvl=2&lvlid=53

150
Office of Minority Health. (2024, January 30). Advancing better health through better
understanding for Black and African American communities: Health literacy, health care
access, and culturally appropriate care 2024 reading list.
HHS.gov. https://www.hhs.gov/black-history-month/reading-list/index.html
O’Kane, P., Smith, A., & Lerman, M. P. (2019). Building transparency and trustworthiness in
inductive research through computer-aided qualitative data analysis software.
Organizational Research Methods, 24(1), 104-139.
https://doi.org/10.1177/1094428119865016
Ortlipp, M. (2008). Keeping and using reflective journals in the qualitative research process. The
Qualitative Report, 13(4), 695-705.
Ostrom, E. (2005). Understanding Institutional Diversity. Princeton University Press.
Ostrom, E. (2009). Understanding institutional diversity. Princeton University Press.
Ostrom, E. (2011). Background on the institutional analysis and development framework. Policy
Studies Journal, 39(1), 7 27. https://doi.org/10.1111/j.15410072.2010.00394.xBloomington.
https://ostromworkshop.indiana.edu/pdf/teachin g/iad-for-policy-applications.pdf
Ostrom, E., & Polski, M. M. (1999). An institutional framework for policy analysis and design.
Ostrom Workshop: Indiana University
Ostrom, E., Schroeder, L. A., & Wynne, S. (1994). Institutional Incentives and
Sustainable Development: Infrastructure Policies in Perspective. Westview Press.
OtterPilot. (2024, April 11). Otter.ai - AI Meeting Note Taker & Real-time AI Transcription.
https://otter.ai/blog/otters-new-otterpilot-tm-is-the-smart-aimeeting-assistant-youve-been-
waiting-for

151
Patton, M. Q. (2002). Qualitative Research & Evaluation Methods (3rd ed.). Sage
Publications.
Patton, M. Q. (2015). Qualitative research and evaluation methods (4th ed.). Thousand
Oaks, CA: Sage.
Peterson, A., Charles, V., Yeung, D., & Coyle, K. (2021). The health equity framework: A
science- and justice-based model for public health researchers and practitioners. Health
Promotion Practice, 22(6), 741-
746. https://doi.org/10.1177/1524839920950730
Pietkiewicz, I. & Smith, J. A (2014) A practical guide to using interpretive phenomenological
analysis in qualitative research psychology. Psychological
Journal, 20, 7-14, doi:10.14691/CPPJ.20.1.1
Pinedo, M., & Villatoro, A. (2020). The role of perceived treatment need in explaining
racial/ethnic disparities in the use of substance abuse treatment services. Journal of Substance
Abuse Treatment, 118,
108105. https://doi.org/10.1016/j.jsat.2020.108105
Public housing primary care program. (2021, June 22). National Center for Health in
Public Housing. https://nchph.org/health-and-housing/
Ravitch, S. M., & Carl, N. M. (2021). Qualitative research: Bridging the conceptual, theoretical,
and methodological. SAGE Publications.
Reising, V., Diegel-Vacek, L., Dadabo, L., Martinez, M., Moore, K., & Corbridge, S.
(2022). Closing the gap. The Nurse Practitioner, 47(4), 41-
47. https://doi.org/10.1097/01.npr.0000822572.45824.3f

152
Roediger, D. (2020, July 20). Historical foundations of race. National Museum of African
American History and Culture. https://nmaahc.si.edu/learn/talking-
aboutrace/topics/historical-foundations-race
Ross, P. T., & Bibler Zaidi, N. L. (2019). Limited by our limitations. Perspectives on
Medical Education, 8(4), 261-264. https://doi.org/10.1007/s40037-019-00530-x
Rowlands, J. (2017). Interviewee Transcript Review as a Tool to Improve Data Quality and
Participant Confidence in Sensitive Research. International Journal of
Qualitative Methods, 20, 20. https://doi.org/10.1177/16094069211066170
Rubin, H. J., & Rubin, I. S. (2012). Qualitative interviewing: The art of hearing data.
Thousand Oaks: Sage.
Rudestam, K. E., & Newton, R. R. (2015). Surviving your dissertation: A comprehensive guide
to content and process. SAGE Publications.
Rudolph, L., Caplan, J., Ben-Moshe, K., & Dillon, L. (2015). Health in all policies: A guide for
state and local governments. American Public Health Association.
Sachs, J. D., & World Health Organization. Commission on Macroeconomics and Health.
(2001). Macroeconomics and health: Investing in health for economic development :
Report of the Commission on macroeconomics and health :
Executive summary.
Sanderson, M., Allen, P., Moran, V., McDermott, I., & Osipovic, D. (2020). Agreeing the
allocation of scarce resources in the English NHS: Ostrom, common pool resources and
the role of the state. Social Science & Medicine, 250,
112888. https://doi.org/10.1016/j.socscimed.2020.112888

153
Sandhu, S., Sharma, A., Cholera, R., & Bettger, J. P. (2021). Integrated health and social care in
the United States: A decade of policy progress. International Journal of
Integrated Care, 21(4). https://doi.org/10.5334/ijic.5687
Saunders, B., Sim, J., Kingstone, T., Baker, S., Waterfield, J., Bartlam, B., Burroughs, H.,
& Jinks, C. (2017). Saturation in qualitative research: exploring its conceptualization and
operationalization. Quality & Quantity, 52(4), 1893–1907.
https://doi.org/10.1007/s11135-017-0574-8
Scharf, D. M., Breslau, J., Hackbarth, N. S., Kusuke, D., Staplefoote, B. L., & Pincus, H. A.
(2014). An examination of new york state's integrated primary and mental health care
services for adults with serious mental illness. Rand Health Quarterly, 4(3).
Shenton, A. K. (2004). Strategies for ensuring trustworthiness in qualitative research projects.
Education for Information, 22(2), 63-75.
Smith, J. (2004). Reflecting on the development of interpretative phenomenological analysis and
its contribution to qualitative research in psychology. Qualitative
Research in Psychology,, 1(1), 39-
54. https://doi.org/10.1191/1478088704qp004oa
Smith, J. A. (Ed.). (2003). Qualitative psychology: A practical guide to research methods.
Sage
Smith, J. A., & Fieldsend, M. (2021). Interpretative phenomenological analysis. In Qualitative
research in psychology: Expanding perspectives in methodology and design., 2nd ed. (pp.
147–166). American Psychological Association.
https://doi.org/10.1037/0000252-008
Smith, J. & Firth, J. (2011). Qualitative data analysis: The framework approach. Nurse

154
Researcher, 18(2), 52-62. https://doi.org/10.7748/nr2011.01.18.2.52.c8284 Smith, J. A.,
Flowers, P., & Larkin, M. (2022). Interpretative phenomenological analysis: Theory, method and
research (2nd ed.). Sage Publications.
Smith, J., & Osborn, M. (2008). Interpretative phenomenological analysis. In J. Smith (Ed.),
Qualitative psychology: A practical guide to research methods (2nd ed., pp.
53-80). Los, Angeles, CA: SAGE Publications.
Smith, J., & Osborn, M. (2015) Interpretative phenomenological analysis as a useful
methodology for research on the lived experiences of pain. British Journal of
Pain, 9(1), 41-47. https://doi.org/10.1177/2049463714541642.
Smith, T. Y., Ogedegbe, C., Arredondo, A., Romney, M., Hoffman, J. R.,
Goldfrank, L. R., & Doobay, K. (2021). Reforming the health care system to address
structural racism. Academic Emergency Medicine, 28(9), 1084-
1086. https://doi.org/10.1111/acem.14303
Sundler, A. J., Lindberg, E., Nilsson, C., & Palmér, L. (2019). Qualitative thematic analysis based
on descriptive phenomenology. Nursing Open, 6(3).
https://doi.org/10.1002/nop2.275
Tepper, M. C., Cohen, A. M., Progovac, A. M., Ault-Brutus, A., Leff, H. S., Mullin, B.,
Cunningham, C. M., & Cook, B. L. (2017). Mind the gap: Developing an integrated
behavioral health home to address health disparities in serious mental illness. Psychiatric
Services, 68(12), 1217-
1224. https://doi.org/10.1176/appi.ps.201700063
The Patient Protection and Affordable Care Act of 2010, Pub.L.No. 111-148, 124 Stat.
119 (2010). https://www.govinfo.gov/content/pkg/PLAW-
155
111publ148/pdf/PLAW-111publ148.pdf
Tufford, L., & Newman, P. (2010). Bracketing in qualitative research. Qualitative Social
Work, 11(1). https://doi.org/10.1177/1473325010368316
University of California, San Francisco. (n.d.). Community Health Immersion Program.
Retrieved from https://meded.ucsf.edu/chip
University of Maryland. (2022.). The Freedmen's Bureau act, March 3, 1865. Freedmen and
Southern Society Project - Welcome
Page. https://www.freedmen.umd.edu/fbact.htm
U.S. Census Bureau. (2021, April 26). Historical population change data (1910-2020).
Census.gov. https://www.census.gov/data/tables/time-series/dec/popchange-datatext.html
U.S. Department of Health and Human Services, Office of Disease Prevention and Health
Promotion. (2020). Healthy People, 2030. Home of the Office of Disease
Prevention and Health Promotion - health.gov. https://health.gov/healthypeople/
U.S. Department of Health and Human Services, Office of Disease Prevention and Health
Promotion. (2020). Social determinants of health. Home of the Office of Disease
Prevention and Health Promotion - health.gov. https://health.gov/healthypeople/priority-
areas/social-determinantshealth
Vasileiou, K., Barnett, J., Thorpe, S. et al. Characterizing and justifying sample size sufficiency
in interview-based studies: systematic analysis of qualitative health research over a 15-
year period. BMC Med Res Methodol 18, 148 (2018).
https://doi.org/10.1186/s12874-018-0594-7
Walden University. (2021). The Doctoral Study

156
Guidebook. https://catalog.waldenu.edu/mime/media/7/943/Doctoral
Walden University. (n.d.). Interview Guide Worksheet. Walden University. Retrieved from
https://academicguides.waldenu.edu/research-center/research-ethics/toolsguides
Walden University. (n.d.). IRB Requirements for Selecting Participants (PDF). Walden
University. Retrieved from https://academicguides.waldenu.edu/researchcenter/research-
ethics/tools-guides
Walden University. (n.d.). IRB Verbatim Informed Consent for Practice Interviews
(PDF). Walden University. Retrieved from https://academicguides.waldenu.edu/research-
center/research-ethics/tools-guides
Watkins, K. E., Ober, A. J., Lamp, K., Lind, M., Setodji, C., Osilla, K. C., Hunter, S. B.,
McCullough, C. M., Becker, K., Iyiewuare, P. O., Diamant, A., Heinzerling, K., &
Pincus, H. A. (2017). Collaborative care for opioid and alcohol use disorders in primary
care. JAMA Internal Medicine, 177(10),
1480. https://doi.org/10.1001/jamainternmed.2017.3947
Williams, D. R., & Mohammed, S. A. (2009). Discrimination and racial disparities in health:
evidence and needed research. Journal of Behavioral Medicine, 32(1), 20-
47.
Wilson, M. G., Lavis, J. N., & Guta, A. (2012). Community-based organizations in the health
sector: A scoping review. Health Research Policy and
Systems, 10(1). https://doi.org/10.1186/1478-4505-10-36
Wintrup, J. (2022). Health by the people, again? The lost lessons of Alma-Ata in a community
health worker programme in Zambia. Social Science & Medicine,

157
115257. https://doi.org/10.1016/j.socscimed.2022.115257
Wippold, G. M., & Frary, S. G. (2021). Predictors of health-related quality of life among
African American men. Journal of Racial and Ethnic Health
Disparities. https://doi.org/10.1007/s40615-021-01151-z
World Health Organization. (1998). Patient empowerment.
https://www.who.int/healthpromotion/
World Health Organization. (2019, May 30). Social determinants of health.
https://www.who.int/health-topics/social-determinants-ofhealth#tab=tab_1.
https://www.who.int/health-topics/social-determinants-ofhealth#tab=tab_1
Wrenn, G., Kasiah, F., Belton, A., Dorvil, S., Roberts, K., Mcgregor, B., & Holden, K.
(2017). Patient and Practitioner Perspectives on Culturally Centered Integrated
Care to Address Health Disparities in Primary Care. The Permanente journal, 21,
16–018. https://doi.org/10.7812/TPP/16-018
Yearby, R., Clark, B., & Figueroa, J. F. (2022). Structural racism in historical and modern US
health care policy. Health Affairs, 41(2), 187-
194. https://doi.org/10.1377/hlthaff.2021.01466
Zeh, P., Sandhu, H. K., Cannaby, A. M., & Sturt, J. A. (2012). The impact of culturally competent
diabetes care interventions for improving diabetes-related outcomes in ethnic minority
groups: A systematic review. Diabetic Medicine, 29(10), 1237-
1252. https://doi.org/10.1111/j.1464-5491.2012.03701.x

