


1
EVALUATING THE ROLE OF HEALTH CARE IN MEXICO IN UNDOCUMENTED
IMMIGRATION TO THE UNITED STATES
CHAPTER 1: INTRODUCTION TO THE STUDY
Introduction
Healthcare access in Mexico over a decade has faced some challenges. According
to Pelcastre-Villauerte et al. (2017), 73% of the population in Mexico live below the
poverty line of $10 a day and consequently, they are unable to purchase private health
insurance. The provision of healthcare services in Mexico can be acquired through public
or private insurance, but most of the services are provided under Popular Insurance,
known in Spanish as Seguro Popular (S.P.; Hone & Gómez-Dantés, 2019;
MartinezMartinez & Rodriguez, 2020; Sosa & Sosa-Rubi, 2016).
In May 2003, the government of Mexico established the S.P. to extend quality
healthcare insurance to the poor, under-insured, and uninsured, to address inequities in
quality healthcare access. Unfortunately, the program failed, and many people still lack
health insurance and quality health care services (Hone & Gómez-Dantés, 2019; Sosa &
Sosa-Rubi, 2016). Only 42.2% of the poor who lack permanent jobs are covered by the
S.P. health insurance in Mexico (Martinez-Martinez & Rodriguez, 2020).
The findings of my study will shed light and provide more information on the role of
healthcare in Mexico in undocumented immigration to the United States. The findings of
this study can have positive implications in the field of public policy, because it will add
to our understanding of the relationship between healthcare and immigration and provide
useful information to better guide the debate on healthcare policy. The findings of my

2
study will also reveal how healthcare access in the United States motivates some people
from Mexico to immigrate to the United States in an undocumented status to have access
to quality healthcare. This information will open a new door for further research on how
quality healthcare in the United States can cause undocumented immigration. In this
chapter, I provide an overview of the work by highlighting the background of the study,
the problem statement and purpose, and research questions. I also present the theoretical
foundation of the study, the nature of the study, and its limitations. Finally, I conclude the
chapter with a discussion of the potential significance of the study.
Background of the Study
Inés Ospina (2019), Macías-Rojas (2018), Orrenius and Zavodny (2019), and
Roberts (2017) explained that undocumented immigration had become a major political,
social, and economic problem in the United States over the decade. According to Heslin
(2018) and Hoekstra and Orozco-Aleman (2017), approximately 12 million
undocumented immigrants are living in the United States, making it difficult for the
government to track the population and implement social intervention policies.
Access to quality healthcare is a problem in Mexico. Pelcastre-Villauerte et al.
(2018), Guerra et al. (2018), Hone and Gómez-Dantés (2019), Martinez-Martinez and
Rodriguez (2020), Sosa and Sosa-Rubi (2016) explained that about 55% of the population
in Mexico lack access to quality healthcare insurance even after the implementation of the
S.P. program. According to Sosa and Sosa-Rubi and Hone and
Gómez-Dantés, healthcare access in Mexico increased because of the implementation of
S.P however, there remains several people who are uninsured or underinsured because of

3
lack of financial resources and effective management of the S.P. by the government. My
study will explore the role of healthcare in Mexico in undocumented immigration to the
United States. It will provide in-depth information on lived experiences of undocumented
immigrants to better understand the role of healthcare in undocumented immigration to
the United States. Also, this information can better guide debates on healthcare public
policies.
Problem Statement
In the United States, undocumented immigration has been a major social and
political problem (Robert, 2017). Historically, the long border between United States and
Mexico has been the focus of American government in curbing undocumented
immigration (Inés Ospina, 2019). Nearly 11 million undocumented immigrants are living
in the United States (Heslin, 2018; Hoekstra & Orozco-Aleman, 2017). According to
Passel and Cohn (2019), in 2017, there were 10.5 million undocumented immigrants in
the United States, including 4.9 million Mexicans (47 %), marking the first time that
undocumented immigrants from Mexico fell below half of the total undocumented
immigrants (Passel & Cohn, 2019). There are many reasons people immigrate to the
United States. According to Macías-Rojas (2018) and Robert (2017), the primary reasons
people immigrate to the United States include: employment, fleeing political persecution,
reuniting with family, and the desire to live in a free society.
Due to the social, political, and economic issues, such as an abundance of narcotic
drugs, pressure on social programs, and pressure on jobs associated with undocumented

4
immigration, Congress, in 1996, passed the Illegal Immigration Reform and Immigrant
Responsibility Act (IIRIRA) to reduce the undocumented immigration (Macías-Rojas,
2018). The probability rate of arrest and apprehension of undocumented immigrants has
increased from 40% in 2000 to 55% by 2015; approximately 304,000 undocumented
immigrants were apprehended along the U.S.-Mexican border in the 2017 fiscal year
(Orrenius & Zavodny, 2019). Another effect of undocumented immigration is that
American citizens are divided on the issue of undocumented immigration and the
divisions are along party lines (Robert, 2017).
The nature of health insurance in Mexico and its challenges, such as being
expensive, lack of quality healthcare services, and inaccessibility, have been recently
studied (Hone & Gómez-Dantés, 2019; Martinez-Martinez & Rodriguez-Brito, 2020;
Rivera-Hernández et al., 2019; Sosa & Sosa-Rubi, 2016). There is an existing body of
information on healthcare in Mexico, but that research does not significantly focus on
ineffective health insurance in Mexico and its relation to undocumented immigration in
the United States. This study will fill this gap by contributing to the body of information
needed to address the problem by providing an evidence-based approach to inform public
policy.
According to Pelcastre-Villauerte et al. (2017), in Mexico, 73% of the population
live below the poverty line and face challenges in purchasing private insurance. The
provision of healthcare services in Mexico can be acquired through public or private
insurance, but most of the services are provided under S.P. (Hone & Gómez-Dantés, 2019;
Martinez-Martinez & Rodriguez, 2020; Sosa & Sosa-Rubi, 2016). In May 2003, the

5
government of Mexico established the S.P. to extend quality healthcare insurance to the
poor, under-insured, and uninsured, to address inequities in quality healthcare access. This
was done through the 1983 amendment of Article 4 of the Mexican Constitution to
provide universal health care for every citizen (Guerra et al., 2018). Unfortunately, the
program failed, and many people still lack health insurance and quality health care
services (Hone & Gómez-Dantés, 2019; Sosa & Sosa-Rubi, 2016).
Only 42.2% of citizens that lack permanent jobs are covered by the S.P. health
insurance in Mexico (Martinez-Martinez & Rodriguez, 2020). The Mexican Institute of
Social Security (IMSS), which provides health insurance for only private companies’
employees, only covered 36.4% of eligible enrollees as many of them wanted to move to
S.P., which is relatively cheaper than the IMSS (Guerra et al., 2018; Martinez-Martinez &
Rodriguez-Brito, 2020). Although there exists evidence that S.P. has increased health
insurance coverage among the underserved, Mexico has one of the highest out-of-pocket
healthcare expenses among the countries belonging to the Organization for Economic Co-
operation and Development (Martinez-Martinez & Rodriguez-Brito, 2020). Despite the
improvement in healthcare insurance, inequities in healthcare provision and utilization
still exist because of lack of finance, personnel, and bureaucracy of the government (Hone
& Gómez-Dantés, 2019; Rivera-Hernández et al., 2019; Sosa & Sosa-
Rubi, 2016).
According to Artiga and Diaz (2019), Castaneda (2016), and Kuruvilla and
Raghavan (2014), even though undocumented immigrants in the United States are denied
healthcare from the Affordable Care Act (ACA) they may obtain low-cost care through

6
community health centers and hospitals that receive federal funding and are required to
screen and stabilize patients who need emergency care, regardless of their immigration
status. Emergency care is backed by the Emergency Medical Treatment and Active Labor
Act (EMTALA) which was first signed into law in 1986 (Kuruvilla & Raghavan, 2014).
Also, in many large medical schools, medical students provide free health care to
members of underserved communities, including undocumented immigrants, as part of
their training rotations (Castaneda, 2016). All these benefits may encourage some
Mexicans to embark on undocumented U.S. immigration to access free or lower-cost
quality health care for themselves and their children. Therefore, it is important to address
Mexico’s inaccessible health insurance to reduce the desire to participate in
undocumented immigration for the purpose to access free or lower-cost U.S. health care.
Purpose of the Study
The purpose of this qualitative study was to understand the role of healthcare
quality in Mexico in undocumented immigration to the United States. I used a
phenomenological approach to engage immigrants from Mexico to explore detailed and
in-depth information on how challenges or problems of health insurance in Mexico could
encourage some Mexicans to cross to the United States to benefit from a free or lower cost
of health care.
I recruited participants who were legal permanent residents and citizens of the
United States but focused on their healthcare access experiences both in Mexico and the
United States before they became legal residents. Smart phone interview was used to
obtain primary data from the participants using principles of confidentiality to protect

7
their welfare. The respondents were selected by using a convenient purposive sampling
strategy (see O’Sullivan et al., 2017; Ravitch & Carl, 2016). My study will include
persons residing in Hidalgo County, Texas.
Research Question
My study intended to answer the following principal research question: What are
the lived experiences of formerly undocumented Mexican immigrants living in Hidalgo
County, Texas, regarding the role of healthcare in their decision to migrate to the United
States?
Conceptual Framework
Lee’s (1996) push and pull theory of migration served as my conceptual
framework. According to Lee, social migration is premised on the push and pull factors
with intervening obstacles in the middle. For the push factors, Lee referred to undesirable
conditions such as poor healthcare, poverty, fear of political persecution, and famine that
force people to leave their homes for other places. The pull factors are conditions such as
good health, peace, good jobs, and prosperity that induce, motivate, and attract people to
places (Lee, 1996). While the push factors are associated with the place of origin, the pull
factors are related to the place of the destination. Lee stated that the decision of a person
to migrate is based on four factors: (a) push factors associated with the area of origin, (b)
pull factors associate with the area of destination, (c) intervening obstacles, and (d)
personal reasons (Lee, 1996). Lee’s push and pull theory of migration is suitable for this
study because it focuses on problems of healthcare insurance in Mexico encouraging
8
people to enter the United States as undocumented to have access to free or lower-cost
quality healthcare services.
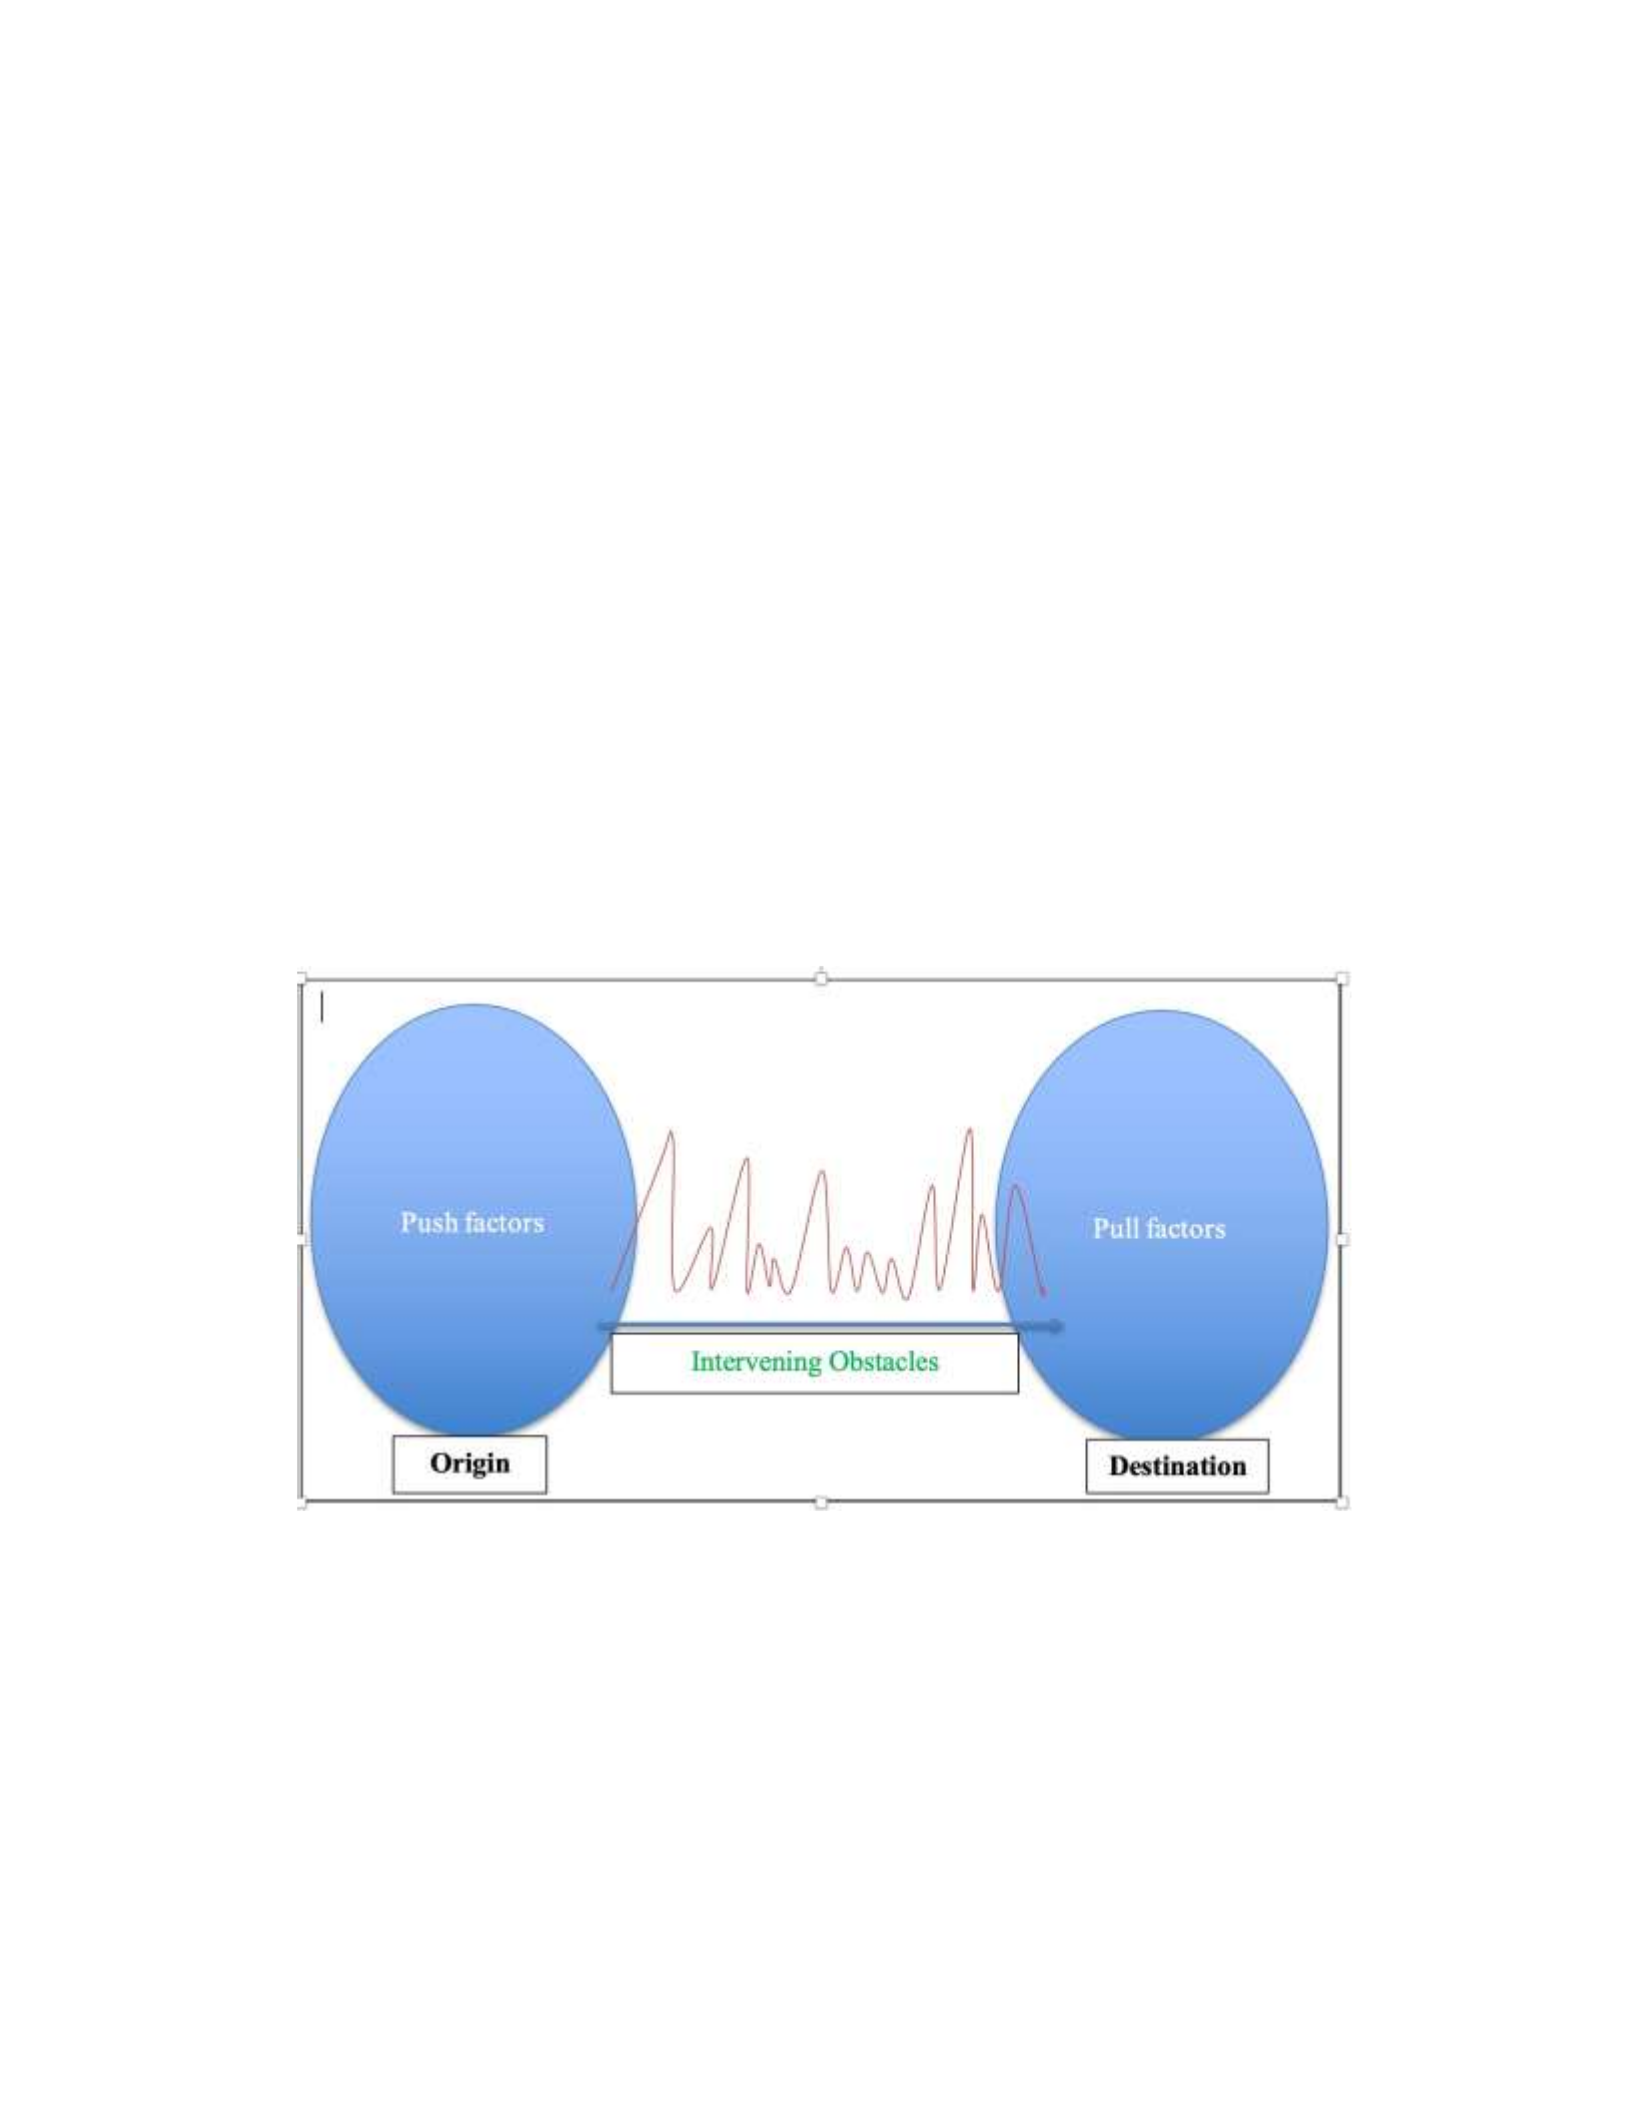
The challenges of health insurance in Mexico may be seen as the push factors and
the free and lower cost of healthcare services for undocumented immigrants in the United
States through limited government programs may be seen as the pull factors as explained
in Lee’s theory. The intervening obstacles may refer to border security, distance, and
transportation challenges. The personal factors refer to the individual perceptions of both
the push and pull factors. Figure1presents the Lee’s model of migration.
Figure 1
Lee’s Model of Migration
Note. The model explains push factors as undesirable conditions at the original place that
discourages people to live there while pull factors at the destination motivate people to
move there. The intervening obstacles are conditions people experience or face during
movement from place of origin to destination.

9
Nature of the Study
My study used a phenomenological approach to examine the “lived experiences”
of migrants who experienced ineffective health insurance in Mexico, leading to
undocumented immigration to the United States. The study included the recruitment of
eligible participants in the United States.
Definitions
Affordable Care Act (ACA): It is officially knowns as Patient Protection and
Affordable Care Act, was passed into law in 2010 to expand the quality and affordable
healthcare to the uninsured and underinsured to promote healthcare accessibility
(Kuruvilla & Raghavan, 2014).
Emergency Medical Treatment and Labor Act (EMTALA): The Act was signed in
1986 stating that patients in emergency rooms must be treated regardless of their legal
status, insurance status, or ability to pay (Kuruvilla & Raghavan, 2014).
Immigration: It is the process through which a person or persons become
permanent residents or citizens of a different country (Parry, 2019).
Migration: It is the movement of people from one location to a particular location
because of push and pulls factors (Lee, 1996).
Push factors: These are issues that impel an individual to emigrate from his/her
country to a different country (Lee, 1996).
Pull factors: These are conditions that motivate a person to migrate to a different
location.
Undocumented immigrants: They are foreign-born individuals living in the United

10
States without authorization (Artiga & Diaz, 2019).
Assumptions
It is assumed that all research participants will participate willingly and honestly.
Another assumption is that all the participants have experienced challenges related to
health insurance in Mexico before becoming undocumented immigrants in the United
States. Participant confidentiality will be assured through the informed consent process
and interview design; therefore, it is assumed all participants will answer questions
truthfully. Finally, based on my background as an immigrant from Africa, I might be
biased in reporting some of the findings, but with my professional background, I should
be able to eliminate personal biases from the findings.
Scope and Delimitations
I recruited participants who are now legal permanent residents and citizens of the
United States but will focus on their healthcare access experiences both in Mexico and the
United States before they become legal residents. This study focused on in-depth
interviews of 7 participants. The research results may not reflect the experiences of all
undocumented immigrants, but it is assumed that it will represent a representative sample
of the target populations’ experiences. Hall (2010) interviewed five homeless individuals
for a phenomenological study on homelessness, and the results of the interviews indicated
that participants’ perceptions and experiences represent the entire homeless population in
the United States.
My study’s main challenge was language barriers. The research participants are
Hispanic, and some can only speak Spanish; a language I do not speak. Therefore, an

11
interpreter was used for participants who spoke Spanish for successful interviews. Also,
the time and location for interviews may pose an inconvenience, which may affect the
quality of the interviews. Another significant concern was the protection of the welfare of
the research participants. The confidentiality of the sensitive information provided by the
participants is paramount and must be abided by. However, divulging confidential
information of the participants through collection and analysis of data may harm the
participants in many ways, including economic, social, and psychological crises. As such,
all data will be reported using participant pseudonyms and aggregated themes apart from
some identity-protected statements that may help to illuminate individual and collective
experiences. My study’s purpose and objectives will be explained to the respondents and
their informed consent form will be obtained. Also, the SARS-CoV-2 (COVID-19)
pandemic may impact participant schedules and appointments, which may affect the
study’s overall timeline. The final limitation is the transferability and dependability of the
research findings as the study is qualitative and employs a non-probability sampling
strategy.
Limitations
I used a phenomenological approach to explore the lived experiences of Mexican
immigrants on the role of quality healthcare in their undocumented immigration to the
United States. One of the study limitations will be the difficulty in ensuring transferability
and dependability of study findings. Even though Lincoln and Guba (1985) and Shenton
(2004) explained strategies to achieve transferability and dependability (generalizability)
for qualitative research, both admitted it is difficult compared to quantitative research.

12
Secondly, I decided to use a nonprobability sampling technique to select participants. This
technique, according to Ravitch and Carl (2016), lacks randomness and enhances the
biases of the researcher. However, Moustakas (1994) argued that the nonprobability
technique can be used in qualitative research because qualitative research focuses on
discovering and providing in-depth information on a topic to provide a better
understanding but not how often something happens. In addressing this, I used a
nonprobability purposive sampling to explore my topic. I also used triangulation, member
checking, and peer debriefing strategies
Significance
My study focused on the role of healthcare in Mexico in undocumented
immigration to the United States. The findings will enlighten people about the role of
healthcare in undocumented immigration to the United Sates. The findings will also have
positive implications for social change in the field of public policy since it will add to our
understanding of the relationship between healthcare and immigration and provide useful
information to better guide the debate on healthcare policy.
Summary
In Chapter 1, I presented the background of the topic. I also detailed the problem
statement, purpose, and nature of the study in this chapter. I concluded Chapter 1 by
outlining the research questions, presented the conceptual framework, explained some
technical terms and research assumptions, outlined the scope and limitations, and finally
discussed the significance. Chapter 2 contains an in-depth literature review on
undocumented immigration, healthcare challenges in Mexico, and the conceptual

13
framework. Chapter 2 also presents a literature review on the research method and
approach. In Chapter 3, I presented information on the design of the research, role of the
researcher, selection of research participants, and instrumentation. This chapter also
covered procedures for data collection, data analysis plan, ethical procedures, and issues
of trustworthiness.
Chapter 2: Literature Review
Introduction
My study focused on exploring the research question: What are the lived
experiences of formerly undocumented Mexican immigrants living in Hidalgo County,
Texas, regarding the role of healthcare in their decision to migrate to the United States?
This chapter presents an approach for reviewing the literature. It includes an outline of the
historical, philosophical, and theoretical perception that entails immigration,
undocumented immigration, migration, and healthcare. The review of the literature starts
with an overview of the historical account of immigration, its effects, and policies put in
place to reduce undocumented immigration. The second section will present scholarly
literature relating to healthcare and its challenges in Mexico as well as healthcare for
undocumented immigrants in the United States. This chapter will also include a review of
the literature regarding the conceptual framework for the study. The final section will
address the literature review related to the approach and methodology.
Literature Search Strategy
For an intensive understanding and illustration of the theoretical and abstract
frameworks of the topic matter, the following databases were conjointly utilized: EBSCO,
ProQuest, ERIC, Google Scholar, and Healthcare Periodicals. I used the following

14
keywords in the search: immigration, undocumented immigration, undocumented
immigration, migration, healthcare insurance, migration theories, and push-pull theory. I
used relevant information from research articles, dissertations, books, seminars, and
organizations websites and the scope of publication year ranges from 1985 to 2020.
Historical Account of Immigration
Immigration is the process of moving to a new country to reside there permanently
(Connor, 2013; Parry, 2019). People who moved to a new country are called immigrants,
but these persons are called emigrants from the old country they moved away permanently
(Conner, 2016). Connor (2016) stated that the United Nations (UN) estimated there to be
232 million international migrants in the world, which is slightly more than 3% of the
world’s population. This percentage would be estimated to represent the world’s fifth-
most populous country if all the world’s migrants were living in a single country (Connor
& López, 2016).
According to Massey (1999), the modern history of international migration can be
divided into four periods: (a) the mercantile period, from 1500 to 1800 in which
immigration was dominated by Europe as a result of colonization and economic growth;
(b) the industrial period, which began from early 1800 to 1925 when more than 48 million
persons left Europe to the Americas and Oceania with a concentration of 85% to five
countries [Argentina, Australia, Canada, New Zealand, and the United States], with the
United States receiving 60 % of the 85% immigrants; (c) period of limited migration,
occurring in the 1930s where the receiving countries, most notably the United States, had
passed restrictive immigration laws because of the Great Depression; and (d) the period of

15
postindustrial migration in the 1960s during which immigration became a global issue
where sending countries like United Kingdom, France, Sweden, Italy, and Portugal as well
as the United States witnessed an overflow of immigrants from the developing countries
into their boarders.
Another history of mass movement of people occurred in Cuba in 1980 and 1994
(Martinez et al., 2015). In 1980, because of political and economic pressure on Cubans,
about 10,000 Cubans invaded the Peruvian Embassy seeking asylum and the Cubans
responded by opening port of Mariel to persons wishing to leave the country (Martinez et
al., 2015. They took the opportunity to decongest the prisons by expelling imprisoned
homosexuals and other prisoners. As a result of this mass immigration, more than 125,000
Cuban refugees arrived in Miami, Florida. Again, in August 1994, about 35,000
Cuban fled to Florida following the rafter crisis (Martinez et al., 2015).
Immigration in the United States
The United States has more immigrants than any other country in the world
(Budiman, 2020; Connor & López, 2016). Between 1880 and 1910 about, 17 million
European immigrants entered United States (Parry, 2019). More than 1 million
immigrants arrive in the United States each year (Budiman, 2020). As of 2015, the UN
stated that the immigrant population in the United States is about 46.6 million (Budiman,
2020; Connor & López, 2016). This represents 19% of the international immigrants. The
immigrant population in the United States is nearly four times that of the world’s next
largest immigrant destination – Germany, with an estimated immigrant population of 12
million (Budiman, 2020; Connor & López, 2016). According to Budiman (2020), in 2020

16
immigrants constituted approximately 13.7% of the U.S. population, 4.8 % in 1970, with
one of the largest migrations in the late 1800’s to fuel the U.S. industrial age. It is
estimated in 1890 that14.8% of the U.S. population, 9.2 million people, were immigrants.
Budiman (2020) further explained that only 77% of the immigrants in the United
States have followed legal processes and the rest are undocumented. It is important to
stress that since the formation of the federal Refugee Resettlement Program by the
Refugee Act in 1980, about 3 million refugees have admitted into the United States, more
than any other country in the world (Budiman, 2020; Connor & López, 2016).
Where Do U.S. Immigrants come from?
The United States of America is being described as the land of immigrants
according to Massey (1999), Parry (2019), and Robert (2017). Every year, about 1 million
immigrants arrive in the United States from all parts of the world; Mexico, China, India,
Philippines, El Salvador, Europe, Canada, Caribbean, Middle East, North Africa, and sub-
Saharan Africa (Budiman, 2020; Connor & López, 2016; Massey, 1999). For the
estimated 46.6 million immigrants of the United States, Mexico is the highest sending
country. In 2018, about 11.2 million (25%) immigrants living in the United States were
from Mexico, 6% each from China and India, 4% from the Philippines, 13% from Europe
and Canada, 10% from the Caribbean, 8% from Central America, 7% from South
America, 4% from the Middle East and North Africa, and finally 5% came from
subSaharan Africa (Budiman, 2020). In recent years new immigrant arrivals in the United
States have declined due to increasing immigration controls (Budiman, 2020; Orrenius &
Zavodny, 2019).

17
Undocumented Immigration
Most people have immigrated to the United States legally, but some have settled in
the country without permission. According to Martinez et al (2015), the term
undocumented immigrant is applicable under the following conditions: (a) legally entered
the country but remained in the country after their visa or permit expired; (b) received
negative remarks on their refugee or asylee application but remained in the country; (c)
experienced changes in their socioeconomic position but could not renew residence permit
but remained in the country; (d) used fraudulent documentation to enter the country; and
(e) unlawfully entered the country. Many of these people were desperate for a job, a better
life, or family reunification (Artiga & Diaz, 2019; Macías-Rojas, 2018;
Parry, 2019)
Robert (2017) explained that undocumented immigration has been considered one
of the major social, economic, and political problems in the United States. According to
Robert, polls conducted over the last 15 years revealed most Americans believe that U.S.
borders are not secured, and that the federal government could do more to reduce
undocumented immigration. As a result of this perception, border security has remained
the most controversial focal point of concern in the United States (Inés Ospina, 2019;
Roberts, 2017).
Nearly 11 million undocumented immigrants live in the United States (Heslin,
2018; Hoekstra & Orozco-Aleman, 2017). Budiman (2020) stated that from 1990, the
population of undocumented immigrants increased from 3.5 million to a high record of

18
12.2 million in 2007. However, by 2017, Passel and Cohn (2019) estimated the
undocumented immigrant population had decreased by 1.7 million, accounting for 10.5
million of which 4.9 million were estimated to be Mexicans. This constitutes 47% of
undocumented immigrants from Mexico in 2017, the first time the undocumented
immigrants from Mexico fell below half of the total undocumented immigrants (Passel &
Cohn, 2019). Budiman added that the 10.5 million undocumented immigrant population
constituted 3.2% of the overall U.S. population in 2017. Between 2007 and 2017 there
was a decrease of the Mexican undocumented immigrants by 2 million leading to an
overall decline of the undocumented immigrants from 12.2 million to 10.5 million in the
United States (Budiman, 2020; Passel & Cohn, 2019).
U.S. Public Perception of Undocumented immigrants
According to Gramlich (2019), a survey was conducted in June 2018 to obtain
opinions about immigrants in the United States. In this survey, only 45% of Americans
said most immigrants are in the country legally, but 35% incorrectly said that most of the
immigrants are in the country in an undocumented status. In another survey conducted
before the 2018 midterm elections among registered voters who planned to vote for
Republican and Democratic Parties, 75% of registered voters who planned to vote for the
Republican candidate said undocumented immigration was a serious problem in the
country against 19% among voters who planned to support Democratic candidate
(Gramlich, 2019). Gramlich also stated that 69% of Republicans agreed that expanding
the wall along the U.S Mexican border is a major restrictive measure to reduce

19
undocumented immigration, but 70% of Democrats indicated that measure would not be
effective in reducing undocumented immigration.
Baranowski (2012) and Krogstad (2020) stated that 74% of U.S. adults said they
favor granting permanent legal status to immigrants who came to the United States as
undocumented. Baranowski added that a survey was conducted among 686 participants
about perceptions of undocumented immigrants from Mexico. The findings revealed that
Latinos have more positive attitudes towards undocumented immigrants than White
Americans. Also, participants with higher education endorsed respect for undocumented
immigrants from Mexico more compared to participants with lower or without education
(Baranowski, 2012). Finally, participants who live within 200 miles of the U.S.- Mexican
border have less tolerant attitudes towards undocumented immigrants from Mexico than
participants who live far away from that region.
Effects of Immigration
There has an overwhelming pressure on healthcare infrastructure in the United
States and one of the causes is the rapid growth of undocumented immigrants (Muschek,
2015). Muschek added that the U.S. federal government spent about $29 billion to take
care of undocumented immigrants in the 2010 fiscal year. Out of this expenditure, $10.7
billion was spent on providing healthcare for undocumented immigrants (Muschek,
2015).
Undocumented immigration has led to an increase in population and an
overwhelming pressure on social welfare programs in the United States (Macías-Rojas,

20
2018; Muschek, 2015; Orrenius & Zavodny, 2019). Kerwin (2018) stated that, between
1997 and 2018, the budget of the U.S. DHS has increased from $1.935 billion to $21.1
billion in efforts to enhance border security and control undocumented entries. This
spending, including expenditure on the healthcare of immigrant children, drains the
federal coffers (Kerwin, 2018). According to Rueben and Gault (2017), when all the costs
of public goods are distributed to everyone in the United States, immigrant adults are
estimated to be more dependent on state and local budgets than native adults. There was a
$2,950 gap difference in budget impact between immigrants and individuals born in the
United States between 2011and 2013.
Borjas (2019) mentioned that from 1990 to 2014 the U.S. Gross Domestic Product
(GDP) would have been 15% less without the contribution and hard work of immigrants.
Borjas further explained that when the immigrants’ population increases by 1%, the
economy of the United States grows by 1.15%. This means that an increase in
immigration has been seen as a great contributor to the economic growth in the United
States. In 2016, foreign-born alone constitutes 16.6% of the labor force in the United
States contributing meaningfully to generating national wealth and output (Borjas, 2019).
According to Desilver (2019), in 2014 27.6 million immigrants were present in the U.S.
workforce of 161.4 million and out of the 27.6 million immigrants, 19.6 million came to
the United States legally; an estimated 8 million are undocumented (Desilver, 2019).
Immigration has been considered as source labor for the United States. In 2014, 33% of
farmworkers were immigrants, 45% of private households were immigrants, and 36% of
the textile and manufacturing industries employed immigrants (Desilver, 2019).

21
Gubernskaya and Dreby (2017) added that, generally, family-based immigration has a
positive impact on the economy of the United States compared to negative effects.
Healthcare and Undocumented immigrants
Flavin et al. (2018) mentioned that 52% of people in the United States believe that
expenditure on immigrants’ healthcare is a great burden on the economy and 67% of the
public hold the belief that undocumented immigrants should not qualify for social services
including healthcare. In the light of this, federal policies have been put in place to deny
undocumented immigrants’ access to public healthcare insurance, Medicare, and Medicaid
(Artiga & Diaz, 2019; Castaneda, 2016; Flavin et al., 2018; Kuruvilla & Raghavan, 2014).
The ACA, which was enacted in March 2010 by Congress to expand access to quality
healthcare, categorically denied undocumented immigrants from being covered (Artiga &
Diaz, 2019; Castaneda, 2016; Flavin et al., 2018; Kuruvilla & Raghavan, 2014). However,
undocumented immigrants may obtain low-cost health care through community health
centers, and hospitals that receive federal funding must screen and stabilize patients who
need emergency care for free regardless of their immigration status. Emergency care is
backed by the Emergency Medical Treatment and Active Labor
Act (EMTALA) which was first signed into law in 1986 (Kuruvilla & Raghavan, 2014).
Also, in many large medical schools, medical students provide free health care to the poor
including undocumented immigrants as part of their training rotations (Castaneda,
2016).
Allyn (2019) stated that California is the first U.S. state to provide state
government-subsidized health benefits to young undocumented immigrants. California,

22
since 2016, has allowed children less than 18 years to benefit from state taxpayer-backed
healthcare regardless of their immigration status (Allyn, 2019). Allyn added that the
lowincome undocumented immigrants aged 25 or younger are being covered by
California’s
Medicaid program.
Recent Efforts to Prevent and Reduce Undocumented Immigration
Due to the sociopolitical and economic issues, such as an abundance of narcotic
drugs, pressure on social programs, and pressure on jobs associated with undocumented
immigration, Congress, in 1996, passed the Illegal Immigration Reform and Immigrant
Responsibility Act (IIRIRA) to prevent or reduce the undocumented immigration
(Macías-Rojas, 2018). Orrenius and Zavodny (2019) stated that about 304, 000
undocumented migrants were arrested along the U.S. – Mexican border in 2017. This is
the lowest rate of apprehension since 1971. Robert (2017) corroborated that successful
undocumented entries in the United States have been reduced by 90% between 2005 to
2015 (from 2 million to 200,000) as a result of enhancing border security ranging from
added personnel to fencing to motion camera detection and the use of aerial surveillance.
The campaign of President Trump during the 2016 elections focused on the
negative effects of immigration included safety, narcotic abundance, rape, and job
security, and called for the need to extend the U.S.-Mexican southern border (Pierce,
2019). According to Pierce (2019), many enforcement measures were undertaken by the
Trump Administration to reduce undocumented immigration included if not all: (a)
National Guard deployment to the U.S. – Mexican border. As of March 2019, about

23
2,100 National Guards troops were still stationed at the border; (b) on April 6, 2018, the
Trump Administration declared a zero-tolerance policy on undocumented immigration
resulting in thousands of children being separated from their families; (c) active-duty
military deployment to the border in October 2018; and (d) increasing border patrol
staffing. In January 2017, President Trump ordered hiring 5,000 additional Border Patrol
officers and by the end of 2018, there were 21,370 officers authorized by Congress
(Pierce, 2019).
On April 29, 2019, the Associated Press reported that Acting Defense Secretary
Shanahan instructed that additional 230 troops be deployed to the southern U.S.-Mexican
border to help Customs and Border Protection (CBP) officers intensify efforts to secure
the border against undocumented entries. This deployment, approved by the Acting
Defense Secretary Shanahan, cost the federal government an estimated $7.4 million. This
money could have been used to address other social and economic challenges (Pierce,
2019).
Healthcare
Baltagi et al. (2017) investigated a relationship between healthcare expenditure
and individual income among 167 countries between 1995 and 2012. Their findings
revealed that healthcare is an essential service rather than a luxury and that the prices of
healthcare services of countries depend on the level of the country’s income distribution.
Lower-income level countries tend to have a higher income elasticity of demand for
healthcare services (Baltagi et al., 2017). The cost of healthcare over the years has

24
increased in the United States and in developing countries alike deterring many people
from accessing healthcare.
During the 67th meeting of the UN General Assembly in New York, all
membercountries passed a resolution in support of universal healthcare systems (Hynes,
2013).
The tenets of the resolution emphasized and encouraged member-countries to provide and
deliver affordable and quality-driven healthcare services to all individuals to help to
achieve the UN Committee’s goals (Hynes, 2013). Hynes added that the resolution
directed member-states to roll out health care policies that do not require healthcare
consumers to pay for important medical services because expensive out-of-pocket
payments can deny poor people quality healthcare access. The UN Committee admitted
challenges facing universal healthcare accessibility but stated that universal healthcare is
worth pursuing as it is the foundation of sustainable development and a means for poverty
reduction. About 150 million people each year face difficulties to pay their medical bills
worldwide and many must sell their assets or go into debt to offset their healthcare bills
(Hynes, 2013).
Murtaza (2020) used the Lee’s push/pull model to explain that United States has
been on top in the world for receiving immigrants since 1970. The immigrants are
motivated to migrate to the United States because of availability of healthcare facilities,
services, and economic opportunities (International Organization for Migration, 2020;
Justice for Immigrant, n.d; Murtaza, 2020). Murtaza further explained that Mexico is the
second largest country of origin for immigrants after India. To collaborate Murtaza, the

25
report of IOM in 2020 stated that 11.8 million Mexicans migrated out of Mexico and 17.5
million Indians left for abroad in 2019. Using Lee’s push and pull theory, Murtaza
demonstrated that people migrated from different places like Africa, South America, and
Asia because of lack healthcare services and facilities to the United States for quality
healthcare services and better life.
Healthcare Access in Mexico
Many countries, including Mexico, still face challenges for ensuring universal
health coverage following the UN’s resolution and the Group of Twenty’s (G20)
declaration and commitment to providing universal health coverage (Hone &
GómezDantés, 2019). Mexico has been in the spotlight related to its effort to expand
quality universal healthcare among its citizens. Hone and Gómez-Dantés (2019),
Martinez-
Martinez and Rodriguez-Brito (2020), Rivera-Hernández et al (2019), and Sosa and Sosa-
Rubi (2016) identified these challenges to include difficulty in examining the term
“universal,” providing “quality healthcare” services, not just access, what type of medical
services to provide, lack of political consensus, and lack of resources. According to
Pelcastre-Villauerte et al. (2017), in Mexico, 73% of the population live below poverty
and face challenges to get insured.
According to Hone and Gómez-Dantés (2019), over the years, Mexico has been
advancing healthcare as a social right, expanding healthcare to the uninsured, and has
invested in infrastructure. The provision of healthcare services in Mexico can be acquired
through public or private insurance, but most of the services are provided under Popular

26
Insurance, known in Spanish as Seguro Popular (S.P.; Hone & Gómez-Dantés, 2019;
Martinez-Martinez & Rodriguez, 2020; Sosa & Sosa-Rubi, 2016). In May 2003, the
government of Mexico established the S.P. to extend quality healthcare insurance to the
poor, underinsured, and uninsured, to address inequities in quality healthcare access. This
was done in line with the 1983 Amendment of Article 4 of the Mexican Constitution to
provide universal health care for every citizen (Guerra et al., 2018).
Unfortunately, the program failed, and many people still lack health insurance and
access to quality health care services (Hone & Gómez-Dantés, 2019; Sosa & Sosa-Rubi,
2016). Only 42.2% of the poor that lack permanent jobs are covered by the S.P. health
insurance in Mexico (Martinez-Martinez & Rodriguez, 2020). The Mexican Institute of
Social Security (IMSS), which provides health insurance for only private companies’
employees, covered only 36.4% of eligible enrollees as many eligible enrollees sought to
be covered under S.P., which is relatively cheaper than the IMSS (Guerra et al., 2018;
Martinez-Martinez & Rodriguez-Brito, 2020). However, the S.P. is not resourceful to
insure them.
Although there exists evidence that S.P. has increased health insurance coverage
among the poor, Mexico has one of the highest out-of-pocket healthcare expenses among
the countries belonging to the Organization for Economic Co-operation and
Development (Martinez-Martinez & Rodriguez-Brito, 2020). Despite the improvement in
healthcare insurance, inequities in healthcare provision and utilization still exist because
of lack of resources, corruption, and inefficiency of the government (Hone & Gómez-
Dantés, 2019; Rivera-Hernández et al., 2019; Sosa & Sosa-Rubi, 2016). Lack of

27
resources, such as inadequate health personnel, finance, and healthcare facilities
especially in the rural areas have affected accessible healthcare in Mexico (Hone &
Gómez-Dantés, 2019; Rivera-Hernández et al., 2019; Sosa & Sosa-Rubi, 2016).
Conceptual Framework
Lee’s push and pull theory served as my research lens. Lee (1996) and Liang
(2006) stated that Ravenstein, who has been considered the originator of the theory of
migration and expert in a social movement, defined migration as moving from one
location to another location as a resident for pressing issues. There are two basic types of
migration; inter-migration (between countries) and intra-migration (within one country;
Lee, 1996; Waldinger et al., 2008). Waldinger et al. (2008) emphasized that the theory of
migration is broadly perceived on basis of international migration which is driven by a
country’s economy, healthcare, political, racial, and cultural identities, and tolerance.
Lee on April 23, 1965, at the Annual Meeting of Mississippi Valley Historical
Association, Kansas City, presented an academic paper on migration and why people
immigrate or emigrate (Lee, 1996). Lee explained that social migration is premised on the
push and pull factors with intervening obstacles in the middle. For the push factors, Lee
referred to undesirable conditions such as poor healthcare, poverty, fear of political
persecution, and famine that force people to leave their homes for other places. The pull
factors are conditions such as good health, peace, good jobs, and prosperity that induce,
motivate, and attract people to places (Lee, 1996). While the push factors are associated
with the place of origin, the pull factors are related to the place of the destination. Lee
stated that the decision of a person to migrate is based on four factors: (a) push factors

28
associated with the area of origin, (b) pull factors associate with the area of destination,
(c) intervening obstacles, and (d) personal reasons (Lee, 1996).
Murtaza (2020) investigated causes of international migration and used Lee’s push
and pull theory as a framework. In this work Murtaza mentioned availability of healthcare
services as a pull factor for migration to the United States and lack of quality healthcare
facilities as push factor. Wurie (2012) also used Lee’s push and pull model to demonstrate
reasons Latinos in Cuba, Mexico, and El Salvador came to the United States. Justice for
Immigrants (2017) also used Lee’s push and pull theory to illustrate the difference
between push and pull factors on international immigration. Faridi (2018) explained that
Lee’s theory of push/pull is one of the best models of theories of migration. Faridi added
that the push/pull theory examined causes of migration both at the place of origin and
destination. Faridi further implied that lack of healthcare services may push people out of
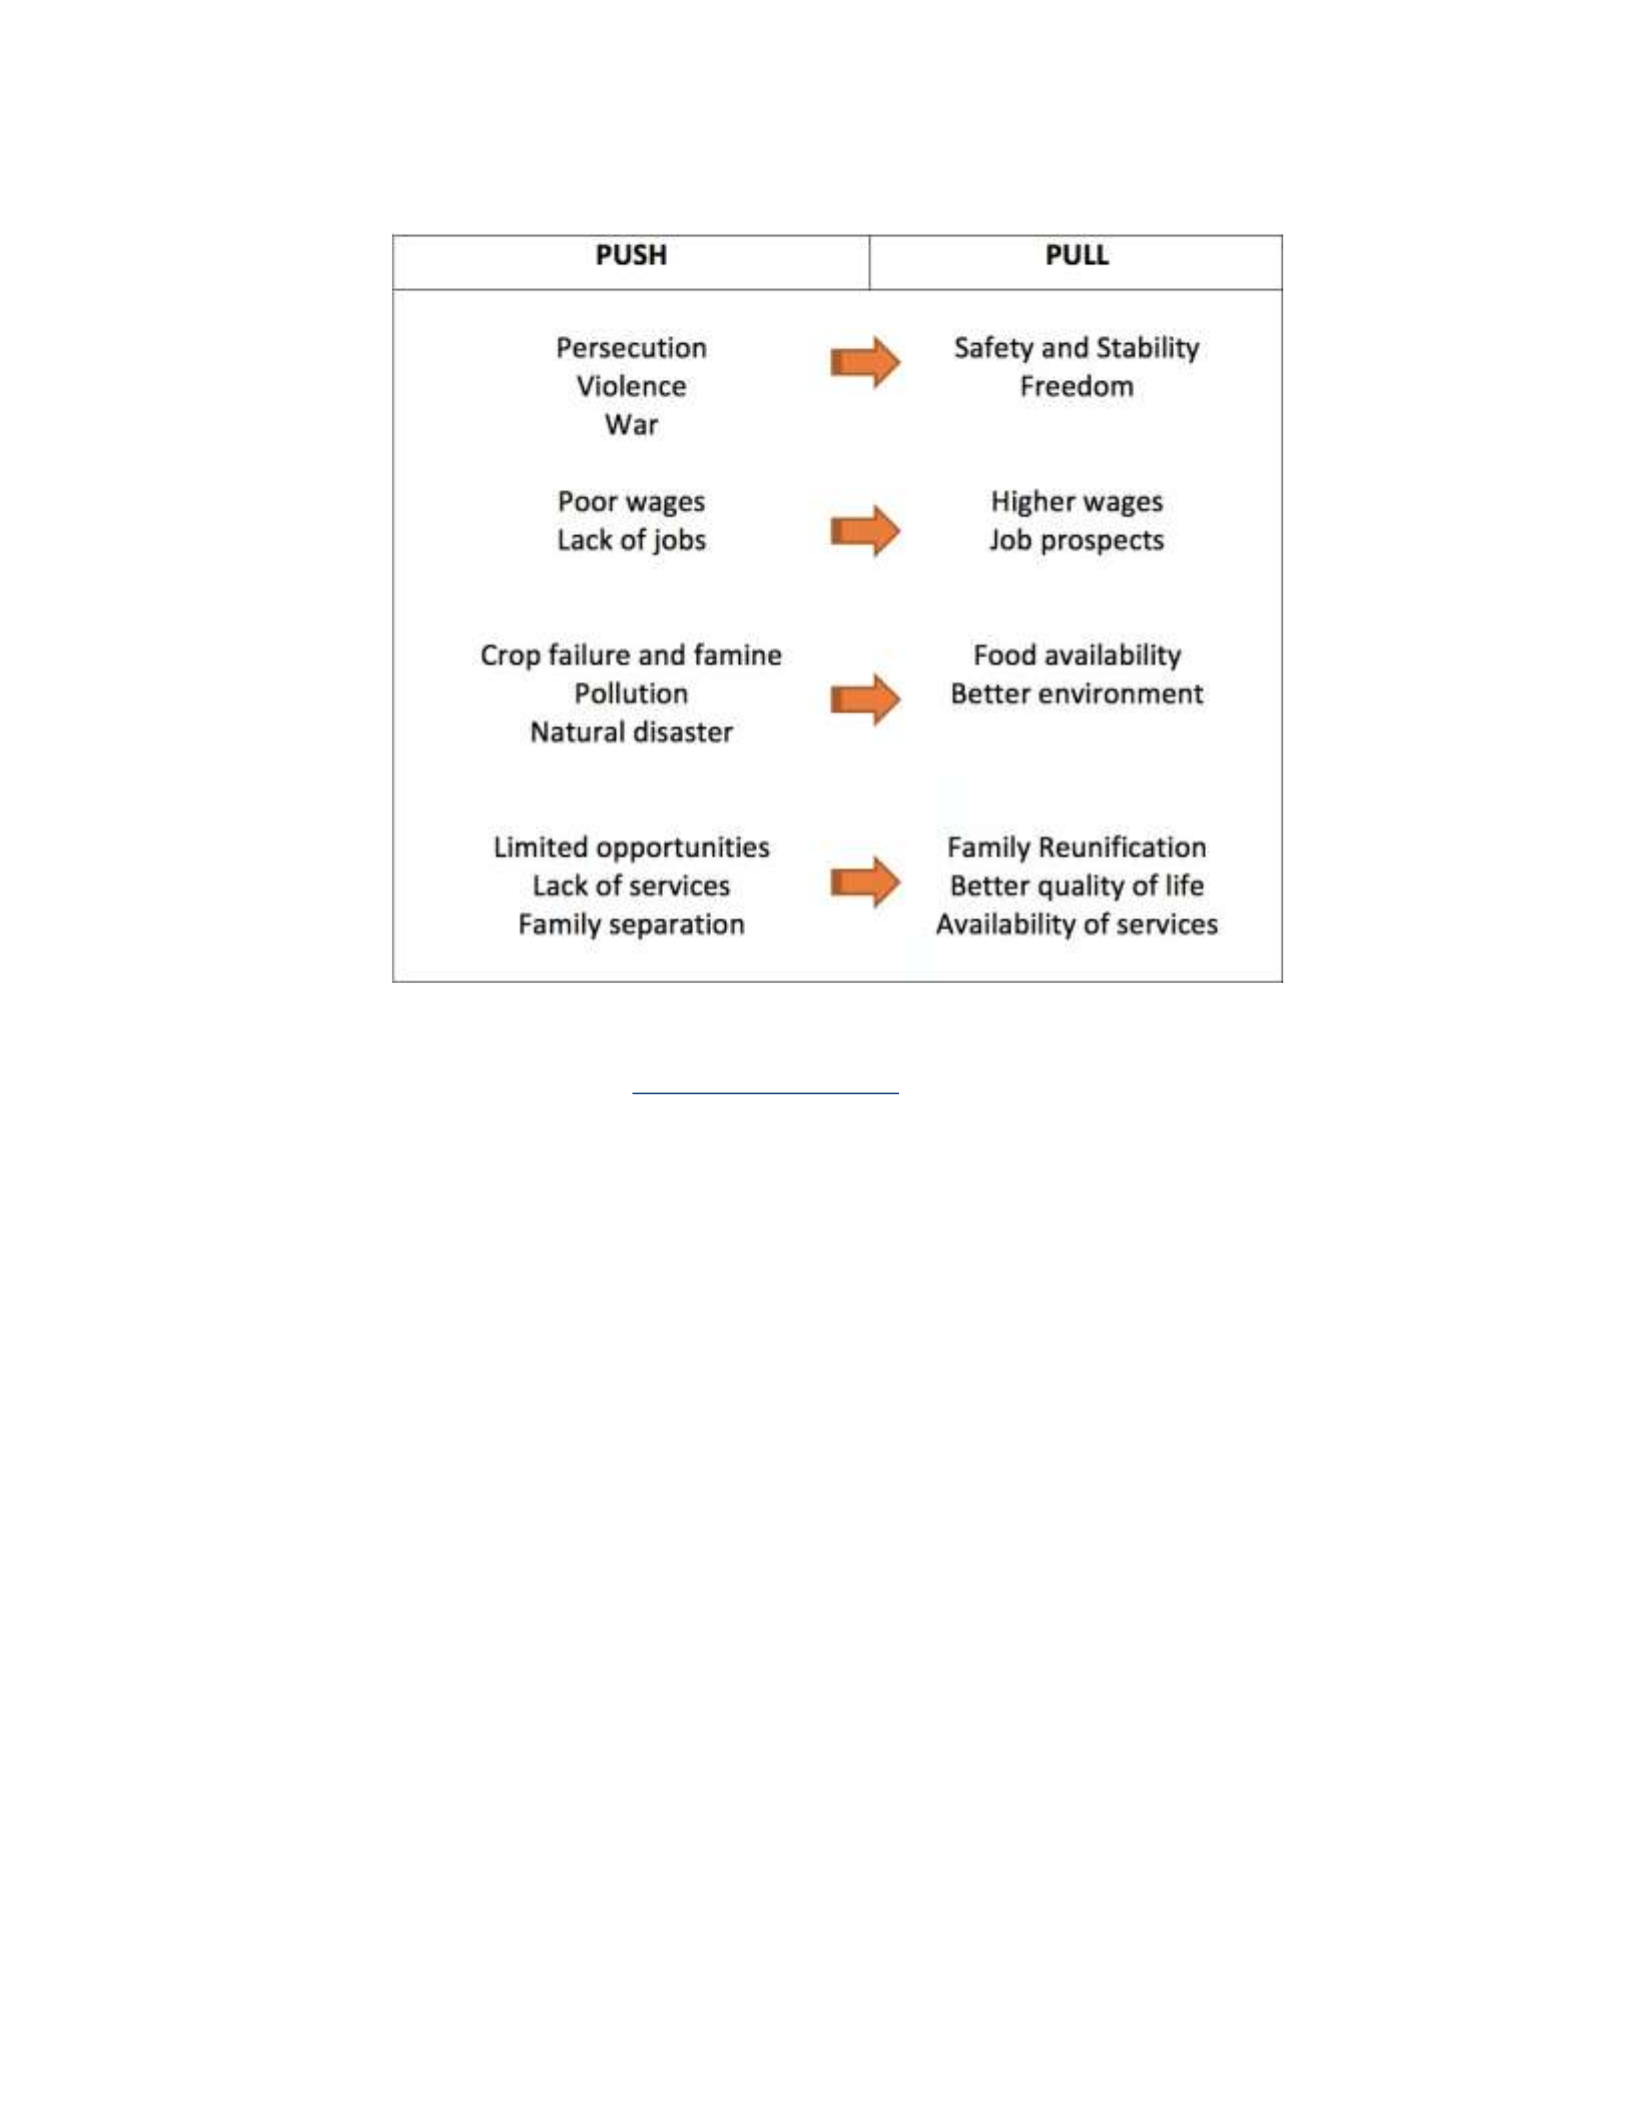
their places and available healthcare services attract immigrants as a pull factor. Justice for
Migrants (2017) illustrated how lack of healthcare services and availability of healthcare
services can serve as push and pull factors under Lee’s theory (See Figure 2).
Figure 2
Push/Pull Factors of Immigration
29
Note. Lack of services as push factors refers to lack of quality healthcare services and
facilities in original location. From “Root Causes of Migration” by Justice for
Immigration, 2017, https://justiceforimmigrants.org/what-we-are-
workingon/immigration/root-causes-of-migration/#_edn14. Public Domain.
Problems of accessing healthcare insurance in Mexico may be encouraging people
to enter the United States as undocumented immigrants to have access to free or lowercost
quality healthcare services. The challenges of health insurance in Mexico may be seen as
the push factors and the free and lower cost of healthcare services for undocumented
immigrants in the United States through limited government programs may be seen as the
pull factors as explained in Lee’s theory. The intervening obstacles may refer to border
security, distance, and transportation challenges. The personal factors refer to the
individual perceptions of both the push and pull factors.

30
Methodology and Approach
I employed a phenomenological approach to explore and examine lived experience
of the research participants on the quality of healthcare in Mexico in undocumented
immigration to the United States. According to Denzin and Lincoln (2008), Husserl was
considered the father of phenomenological approach because he used the approach to
conduct many research studies on the behavior and lived experiences of people.
Moustakas (1994) phenomenology research makes it possible for a researcher to actively
engage participants to explore lived experience on concerning social issues. Moustakas
further explained that under phenomenological research, a researcher should focus on
personal observations, participants’ experiences, and emotions to make meanings.
Phenomenological research also focuses on listening, documenting, and interpreting lived
experiences and behaviors in real life (Moustakas, 1994; Patton, 2015; Ravitch & Carl,
2016; Sloan & Bowe, 2014). Moustakas and Ravitch and Carl (2016) summarized
phenomenology characteristics to include: (a) focuses on meanings of lived experiences,
(b) aligns with qualitative research method, (c) does not predict relationships between
variables as in quantitative research, (d) the approach fully engages research participants
attention as they account their experiences, and (e) the approach focuses on meanings and
not how frequently an event occurs or is repeated.
Wurie (2012) conducted a qualitative study and used the phenomenology approach
with 7 participants. The study focused on exploring the lives of Salvadoran families after
the implementation of IIRIRA. This study is similar to my study as both focus on
exploring lived experience of a particular group of people (immigrants) in the United

31
States. While Wurie’s population was the Salvadoran community, mine will target the
Mexican immigrants in the United States. Hall (2010) employed a phenomenology
approach to understanding the challenges of homeless individuals towards
selfindependence. Hall also used this approach to elicit lived experience of homeless
people as I intend to use it to understand lived experience of immigrants on healthcare
insurance challenges in Mexico to undocumented immigration in the United States.
Finally, another important literature review on the approach is the work by Davis and Erez
(1998). These authors used a phenomenology approach to examine the lived experiences
of immigrants towards the multicultural criminal justice system in the United States. I
have the same reason to use the phenomenology approach as the authors, but the
difference is the target population. For these notions, I used a phenomenology approach to
provide in-depth accounts of Mexican immigrants on healthcare insurance challenges in
Mexico to undocumented immigration in the United States.
Summary and Conclusion
As articulated in chapter 2, undocumented immigration has been an issue in the
United States and nearly 11 million undocumented immigrants are living in the United
States making it difficult for the government to track the exact population. The growing
number of undocumented immigrants over the decades has put pressure on social service
and welfare programs and the inflow of narcotic drugs through the southern U.S.Mexican
border. This chapter presented a literature review on focused immigration patterns,
specifically undocumented immigration to the United States, and its effects and efforts
made to prevent or reduce undocumented immigration by the Trump

32
Administration.
This chapter also covered a literature review of healthcare insurance in Mexico
and its challenges. Lee’s push and pull theory served as my conceptual lens. The theory
posits that people begin to move to different places because of push and pull factors. Lee’s
push and pull theory is appropriate and aligns with the purpose of the study. The study
focused on exploring undocumented immigrants’ experience on the role of quality
healthcare in undocumented immigration to the United States. Chapter 3 contains
information describing my methodological approach to explore the lived experience of
undocumented U.S. immigrants. Chapter 3 outlines the research design, sample size,
processes for participant selection, instrumentation, the procedure for data collection,
plan for data analysis, ethical issues, and issues of trustworthiness.
Chapter 3: Research Methodology
Introduction
This study relied on a phenomenological research approach to elicit a detailed
lived experience of Mexican immigrants on problems of health insurance in Mexico as a
driver for undocumented immigration to the United States. I explored the lived
experiences of adults who have immigrated to the United Status in a previous
undocumented status to provide an in-depth look at information regarding healthcare
access as a driver for their immigration journey. This chapter elaborated on the research
questions, interview questions, qualitative methodology, role of the researcher, procedures
of data collection, ethical concerns, phenomenology inquiry, validity, reliability, and
conclusion.

33
Research Design and Rational
Research Question
The main research question was: What are the lived experiences of formerly
undocumented Mexican immigrants living in Hidalgo County, Texas, regarding the role of
healthcare in their decision to migrate to the United States?
Qualitative Method
I relied on a phenomenological design to investigate the lived experience of
Mexican immigrants on the role of health insurance problems in Mexico in relation to its
push factors for undocumented immigration to the United States. Denzin and Lincoln
(2009), O’Sullivan et al (2017), Patton (2015), and Ravitch and Carl (2016) opined that
phenomenological focuses on eliciting and interpreting lived experiences and narrations
while the quantitative method is appropriate for studies that focus on testing hypotheses to
understand causal relationships between variables or phenomena. O’Sullivan et al and
Ravitch and Carl did further explain that the choice of research method is determined by
the nature of the research question. If the research question is exploratory and seeks to
provide in-depth information about a problem, the appropriate research method is
qualitative (Denzin & Lincoln, 2009; O’Sullivan et al., 2017; Ravitch & Carl, 2016).
Based on this and the purpose of my research, the appropriate method I used is the
qualitative method.
Phenomenological Research
Phenomenology is one of the approaches of qualitative research. It focuses on
listening, documenting, and interpreting lived experiences and behaviors in real life

34
(Moustakas, 1994; Patton, 2015; Ravitch & Carl, 2016; Sloan & Bowe, 2014). According
to Denzin and Lincoln (2008), Husserl was considered the brainchild behind the
phenomenology approach as he used the approach to conduct research on the behavior
and experiences of people. Moustakas (1994) explained that under phenomenological
research, a researcher should focus on personal observations, participants’ experiences,
and emotions to make meanings. McNabb (2008) added that phenomenology is utilized in
social research to find social meanings of problems, activities, arts, and work. This has
justified my intention to use the approach to explore lived experiences of Mexican
immigrants on the role of healthcare quality in undocumented immigration to the United
States.
The Role of the Researcher
My interest is to involve communities in identifying social problems related to
healthcare and finding solutions to the problems through empirical inquiry. I used
interviews to elicit lived experiences of the research participants. My role in the process
was to recruit participants, interview them using a semistructured question list, listen and
record findings that conveyed their feelings and lived experiences in relation to the role of
healthcare insurance in Mexico in undocumented immigration to the United States.
Participant Selection
All participants reside in Hidalgo County, Texas, United States, and initial
recruitment was conducted using a social media platform in which I posted my research
interest in English and Spanish on my personal page seeking participants (see Appendix
A). The target population was legal immigrants from Mexico who entered the United

35
States in an undocumented immigrant status. I used a convenient purposive sampling
technique for recruitment. A convenient purposive technique allows the researcher to
select participants who are knowledgeable and have in-depth information about the topic
(Ravitch & Carl, 2016; Rubin & Rubin, 2012; Sharma, 2017). Individuals who responded
to either the English or Spanish social media recruitment posting were contacted using
direct messaging in the social media application and provided further contact details to
review study inclusion criteria and informed consenting procedures. Date and time
stamping were captured and chronologically utilized for participant selection in the event
the interest exceeds required participant threshold. If social media recruitment efforts
failed to achieve seven potential participants, I had planned to use a snowball recruitment
strategy to enlist additional participants by asking my participants who have completed
the study interview to inform other people about the study and provide them my contact
information or direct them to the social media posting for direct messaging. This snowball
recruitment strategy was not needed as I was able to recruit and retain all seven
participants during the initial recruitment process.
I used a sample size of seven participants. The justification for this can be seen in
the research work of Wurie (2012), where he used the same phenomenological research
and a convenient purposive sampling technique of a sample size of seven adults to
investigate the awareness of the implementation of 287(g) among Salvadoran immigrants
to explore the awareness of 287(g) policies among Salvadoran immigrants in the United
States. The similarity between my research and Wurie’s study is that I also used both
qualitative, phenomenological approach, and a convenient sampling strategy with seven

36
participants. Rudestam and Newton (2007) stated that a recommended sample size for
phenomenological research should range between five to 30 participants. According to
Creswell (2007) the recommended sample size for a phenomenological study is between
five to 25, as far as saturation is concerned. Saturation according to Mason (2010) is the
amount of quality information a researcher needs to provide a detailed and clearer picture
about a topic. Morse contends that a minimum of six participants are required for a
proper phenomenological study to be conducted (Mason, 2010). Therefore, my sample
size was seven participants. Another reason is that qualitative study focuses on credible in-
depth information, but not frequencies and generalizations (Mason, 2010; Ravitch &
Carl, 2016).
I understand the vulnerable nature and welfare of the participants. The
immigration legal status of the participants makes them vulnerable and revealing this
confidential information will subject them to possible legal suits, jail time, and
deportation. To protect and keep them safe, I will not reveal any information on their legal
status nor reveal any confidential information that may jeopardize participants’ welfare. I
will assign participant pseudonyms to conceal their identities.
Instrumentation
I used phone interviews to explore my research question. Smart phone and internet
platform interviews were conducted using a qualified Spanish interpreter for participants
wishing to conduct their interviews in Spanish. Using a three-way smartphone calling
feature, I initiated a call first with my Spanish interpreter and then add the participant to
the call. The participant was asked if they wish to conduct the interview in English or

37
Spanish. For those expressing their request to conduct in English, the Spanish interpreter
exited the group call. For those wishing to conduct the interview in Spanish, the interview
proceeded with the Spanish interpreter present. For interviews conducted using an
internet-based connection tool each attendee will be provided a conference access link to
join at the prearranged access time. Interviewing is one of the many ways to collect data
for qualitative studies (Jacob & Furgeson, 2012; Rubin & Rubin, 2012). Interviewing is
the most appropriate tool because my study uses a phenomenology method, which focuses
on exploring in-depth human experience with interest phenomenon (Patton, 2015). The
semistructured interview gives participants enough time and flexibility to expand their
answers and provide detailed information (Rubin & Rubin, 2012). It also allows the
researcher to ask probing or follow-up questions for clarity (Rubin & Rubin, 2012). On
these notions, I used a semistructured interview to explore my participants' lived
experiences and allow them to provide indepth information on the topic. But Ravitch and
Carl (2016) and Rubin and Rubin (2012) cautioned that researchers using semistructured
interviews should remain focused and take control of the process in line with the research
question. According to Jacob and Furgeson (2012), interviewing makes it possible for
participants to share their stories in detail for quality information.
I formulated my interview questions (see Appendix B) to align with my research
question based on the existing interview question from existing scales and studies and the
tips provided by Jacob and Furgeson (2012). I also reframed some focus group interview
questions of Betancourt et al. (2015) for Somali refugees to create the first, second, and
third questions. I also revised interview questions on accessible healthcare in Mexico

38
(Martinez-Martinez and Rodriguez-Brito,2020) to formulate question 2 and 3. I
formulated question 4, 5,6,7, and 8 based on Lee’s push and pull theory, the work of
Murtaza (2020), and Wurie (2012).
The first question of the interview questions intended to gather information about
the background of the respondents. Jacob and Furgeson (2012) explained that the
background questions help the researcher to warm up participants and facilitate the
selection process. The information I obtained help me to determine whether participants
have met selection criteria based on age and birthplace or country of origin. The second
and third questions dealt with accessibility of health insurance in Mexico and its
challenges. Question four covered the benefits of healthcare in the United States and how
they motivate immigrants as pull factors. The fifth question sought information about how
participants came to the United States because of cheaper and accessibility to healthcare.
The final question centered on the differences between health insurance accessibility in
Mexico and health insurance accessibility in the United States.
Interview questions should be open-ended and clear to understand (Ravitch &Carl,
2016; Rubin & Ruin, 2012). The questions should not be leading respondents to specific
responses, nor should clues about possible responses be embedded within them (Rubin &
Rubin, 2012). The construction of the interview questions should not contain words that
may trigger passions, inflate emotions, or disrespect respondents (Rubin & Rubin, 2012).
The other data sources I included are declassified information from the website of U.S.
DHS regarding undocumented immigration on the southern border. This created an

39
opportunity for triangulation of all the sources of data for valid and credible data
(Shenton, 2004).
Procedures for Data Collection
Following the recruitment process above, I emailed an informed consent in both
English and Spanish wherein the purpose of the research is explained in more detail to
include participants’ rights and the voluntary nature of their participation to include the
right to withdraw from the interviews at any time and the right to skip any question they
feel uncomfortable answering. Participants could schedule the interview for their
convenience after they agree to participate.
According to Rubin and Rubin (2012), recording and transcribing or taking notes
of interviews help the researcher minimizes biases and produces credible findings. I
sought permission to audio record and transcribe the interviews for credible data. I used
the Call Recorder smartphone application to digitally capture telephone interviews for
transcription. For interviews being conducted using internet connectivity tools, I used the
embedded recording features in the digital product to produce data transcripts. For
confidentiality purposes when using an internet-based connecting tool, participants were
advised that they may keep their video cameras off. For those participants who decline to
be audio recorded either during smartphone or interview-based connections, I took
detailed notes throughout the interview process. Participant pseudonyms are used for
confidentiality purpose.

40
Data Analysis Plan
I used the Call Recorder application to record and transcribe phone interviews and
I used embedded voice recording features of internet-based connection tools for
interviews conducted using these interfaces. I took interview notes for those sessions in
which audio recording was declined. Transcription of interviews helps the researcher to
have a vivid understanding of what transpired during interviews and captures exactly what
each participant says (Rubin & Rubin, 2012). Following transcription construction,
I used ATLAS.ti software for coding and data analyses. According to Rubin and Rubin
(2012), coding is one of the first key elements of qualitative data analysis and
interpretation. The ATLAS.ti software is one of the leading software qualitative data
analyses (QDA) tools and it provides researchers with a broad scope of informative
details related to their phenomenon of interest (Boston University, n.d; Predictive
Analysis Today, 2016a). ATLAS.ti also allows researchers to gain in depth information
and to see content patterns bringing meaning to information (Boston University, n.d;
Predictive Analysis Today, 2016a).
Ethical Consideration
My participants are considered vulnerable immigrants and, as such, issues of
privacy and confidentiality are very important. All participants are anticipated to be in a
legal U.S. resident status at the time of interviews. Participants may choose to discuss or
describe their immigration journey; however, I had not explored specific information
regarding immigration status in my interview questions. Informed consent was used to
describe participant rights. Creswell (2007) stated that a researcher should explain the

41
purpose of a study to participants to gain their trust. Participants were assigned
pseudonyms for confidentiality. To achieve this, I allowed participants to choose unique
alphabets other than their real names to conceal their identities. If the selected alphabet
has already been adopted by another participant in a concluded interview, I ask the present
interview participant to select another alphabet. Creswell added that the true names of
participants should not be used to enhance their privacy and confidentiality. I explained to
each participant my study’s purpose and remind them that participation is voluntary, and
any participant is free to quit at any stage of the investigation. According to Ravitch and
Carl (2016) and Rubin and Rubin (2012), it is unethical to lie to participants about a
study’s purpose or force any person to participate in research. My interview questions
were constructed as open-ended questions and were not expected to demean or trigger
respondent emotions. Data protection is the process of ensuring the security of
information obtained from participants to guarantee their safety (Rubin & Rubin, 2012) To
ensure data protection, I removed all information or cues on interview transcript that
might reveal participants’ identity. I only shared the redacted findings and analysis with
the Walden University’s faculty members. I securely stored the contact information of
participants, data, and study analyses on electronic files in Dropbox with a backup file
stored on an encrypted flash drive. I secured the flash drive in my locker I will keep and
protect the data for at least 5 years as required by Walden University. At the conclusion of
the required 5-year storage period, I will destroy electronic data using a disc wipe
software and all information contained on paper will be shredded.

42
Member Checking
I provided each participant an opportunity to member-check their transcriptions to
ensure information has been clearly captured and to validate that confidentially has been
maintained. According to Guba and Lincoln (1985), the member checking technique
allows research participants to check and confirm their answers for credibility and true
representation. After each interview, I gave 30 minutes to each participant to check all
their answers to make sure it is what they want to say. For participants who do not wish to
participate in member checking their transcripts will be accepted as final and used for
analyses. Wurie (2012) used member checking technique to enhance and strengthen data
credibility.
Issues of Trustworthiness
The credibility of qualitative data is equally important as it is in a quantitative
study (Shenton, 2004). For the data of qualitative research to be trustworthy, the
information obtained in the field should be credible, transferable, dependable, and
confirmable (Shenton, 2004). Credibility is the process of revealing what exactly
happened in the field (Shenton, 2004). To obtain credible data, a researcher should use the
triangulation strategy, member checking, peer debriefing, and observation (Shenton,
2004). Lincoln and Guba (1985) and Shenton (2004) explained triangulation as using
many sources of data collection to check inconsistencies. Apart from the interviews, I will
access data from the websites of U.S. DHS, Mexico Health Department, and U.S. BPC to
check insistencies for credible data. I used a colleague student at Walden who is interested
in the topic for peer debriefing. I posted the announcement on Walden students’

43
dissertation groups on Facebook for interested person. The person sent me a private
message on Facebook messenger accepting to debrief my findings. We are not acquainted.
The person signed a confidentiality agreement and focused mainly on checking my
personal biases and perceptions. The debriefing process started soon after interviews were
conducted and ended after data analysis. I emailed the interview notes or transcripts to the
person. I used the member checking technique and according to Shenton, member
checking allows participants to make corrections to reflect what they wanted to say to
make sure the information provided is true.
To achieve transferability which refers to where the findings of one study can be
used in different settings (Lincoln & Guba, 1985; Shenton, 2004), the researcher should
allow participants to provide detailed information about the topic to generalize findings
(Lincoln & Guba, 1985; Shenton, 2004). This is in line with my selected
phenomenological approach. To achieve dependability, which refers to findings being
consistent and can be replicated (Lincoln & Guba, 1985; Shenton, 2004) semistructured
interviews were used to allow participants provide detailed information about the topic.
Finally, the last requirement to ensure data trustworthiness according to Shenton (2004) is
confirmability. This is where the researcher should be neutral to prevent biases and
provide an audit trail of all for the research (Lincoln & Guba, 1985; Shenton, 2004). The
triangulation method also enhances the confirmability of a study (Lincoln & Guba, 1985;
Shenton, 2004) which I employed.

44
Summary
Chapter 3 presented information on the design of the research, role of the
researcher, selection of research participants, and instrumentation. The study’s design is
phenomenology. Convenient sampling is used to select research participants. Recruitment
of participants was done on social media. Interviews were conducted using phone and
other internet-based electronic tools. ATLAS.ti software is used for data coding and
analyses. This chapter additionally described my study’s ethical procedures and issues of
trustworthiness for recruitment, interviewing, coding, and analyses.
The Chapter 4 presents findings of my in-depth interviews, data analyses, and
evidence of trustworthiness of the data collected. The chapter also presents characteristics
and information about the research participants. In this chapter, the responses provided by
the research participants are categorized into themes for easy analysis and understanding.
Chapter 4: Research Findings
Introduction
The study’s purpose was to understand the role of healthcare quality in Mexico in
undocumented immigration to the United States. A phenomenological research approach
was used to explore lived experiences of the research participants. This chapter presents
information about the research participants, their experience with undocumented
immigration to the United States, and healthcare in both Mexico and United States. The
chapter also presents research findings and data analysis.

45
Setting
All the interviews were conducted via phone. In total, seven participants were
interviewed; five participants agreed to speak to me in English while two participants
opted to do the interview in Spanish through the interpreter. Each interview lasted about
45 minutes and additional 30 minutes for member checking was needed once individual
transcripts were transcribed, cleaned, and formatted for sharing with the interviewed
participant.
After I received IRB approval (0986362; 05-26-22), I recruited all the seven
participants using a social media platform. I posted my recruitment announcement
(Appendix A) on my personal page wall. The people who had interest to participate
responded to the posting through direct messaging to my user account name. I then
provided them criteria for recruitment and the informed consent. Each of the seven
recruited participants completed the research interview in its entirety. I made no changes
to the informed consent after IRB approval as I did not change participants’ recruitment
process, data collection methods, analysis, and data storage.
Demographics
All seven study participants lived in the Hidalgo County, Texas, United States.
All the participants are adults who experienced healthcare both in Mexico and United
States. All participants speak English and Spanish and used to have jobs in Mexico. Out
of seven participants only two people did their interview in Spanish. To ensure
confidentiality, I used pseudonyms for all participants interviewed.
John
At his interview time, John was living in Hidalgo County, Texas. He is in his mid

46
40s and currently a truck driver in the United States. He came to the United States from
Mexico. He was truck driver too in Mexico. He had health insurance in Mexico and
currently has health insurance in the United States. John sent me a message to take part in
the study after reading the recruitment posting I posted on my social media page
(Appendix A). During the interview phone call, he declined the interview be
audiorecorded and agreed the interview to be conducted in English. John was polite and
clear during the entire process.
Juan
At his interview time, Juan was living at Hidalgo County, Texas and working as
car mechanic. He is in his early 40s. He immigrated to United States from Mexico in his
early 30s at Tamaulipas closer to the southern border. Juan was a car mechanic in Mexico.
He was fully insured at the time of this study. Juan sent me message after he read my
recruitment posting I posted on my social media page. He turned down my request to
audio-record his interview. He requested the interview to be conducted in Spanish through
the interpreter. His interview was done in Spanish. Juan was nervous when he answered
the interview phone call, but he became calm and relaxed when I started building rapport
and asking questions about his favorite food and car for the first 5 minutes. He was
comfortable, articulate, and audible in Spanish language. His interview lasted about 45
minutes.
Maria
At her interview time, Maria was residing at Hidalgo County, Texas and working
as a nurse. Maria is in her late 40s. In Mexico she was living at Reynosa a city closer to
the Mexican-U.S. border. She came to the United States in her early 30s. She was a nurse

47
in Mexico. Maria who saw my recruitment post in Spanish on my social media page and
sent me a message expressing interest to participate. Before her phone interview started,
Maria explicitly stated he wants the interview to be conducted in Spanish and should not
be recorded. Maria was happy throughout the interview process and was straight forward
in her responses. She was clear. Her interview lasted about 50 minutes.
Rosa
At her interview time, Rosa was residing at the Hidalgo County, Texas. Rosa was a
teacher in Mexico before coming to the United States and she had health insurance. She is
in her early 40s and teaches in middle school in the United States. She immigrated from
Palau Coahuila. Rosa replied to my recruitment post on my social media page and sent me
message expressing her interest in the study. During the phone interview call, she agreed
that the interview should be conducted in English but should not be recorded. She was
clear and detailed in her responses to the interview questions and answer all the questions.
Her interview lasted for about 30 minutes.
Perez
He is in his mid 70s. At his interview time, Perez was living in Hidalgo County,
Texas. He was born in Mexico, but he immigrated to the United States in his early 40s.
He was a welder in Mexico for more than 40 years. He had health insurance in Mexico.
Perez was working as a welder when he arrived in the United States, but now he is retired.
Perez sent me a message after he read my recruitment post on my social media page.
Before the interview started during the interview phone call, Perez opted for English
interview, but turned down my request to record the call. He was so emotional and

48
provided examples for probing questions. He remained calm throughout the interview and
provided concise and clear responses. His interview lasted for about 50 minutes.
Kiara
She is in her late 50s. At her interview time, Kiara was living at Hidalgo County,
Texas and working as nurse. She moved to the United States from Mexico when her
husband had work related accident in Mexico. In Mexico, Kiara used to work in one
factory called Maquiladoras. She had health insurance in Mexico because of her job.
Kiara read my recruitment post (Appendix A) on Facebook and sent a direct message to
me on Facebook. When I called her for the interview, she indicated she wants the
interview to be conducted in English, but she declined the request to record the call. Kiara
was open, detailed, and audible in her responses. The interview with her lasted for about
30 minutes.
Juliana
She is in her mid 40s and at her interview time lives in Hidalgo County, Texas.
Juliana immigrated to the United States from Mexico when she was battling with a
chronic hepatitis B and had medical issues with her liver. Juliana was a working in a
restaurant as waitress. She had healthcare insurance in Mexico. In the United States,
Juliana is working as parole officer. She read my recruitment post on my social media
page and sent me a message to show interest as participant. During the phone interview,
she agreed to speak English and turned down my request to record the call. Throughout
the interview she was calm, happy, and clear. The interview call with Julian lasted for
about 45 minutes.

49
Data Collection
I collected data from seven research participants using the semistructured
interview protocol (see Appendix B) to explore lived experience of the participants. All
the interviews were conducted via phone. Each interview lasted between 30 to 60 minutes.
I scheduled each interview at the convenience and request of each participant. I used 2
weeks to complete the interviews and member checking. Two of the interviews were
conducted in Spanish with professional interpreter and five interviews were conducted in
English. The settings for this were inside my room in Fort Worth, Texas and Hidalgo
County, Texas, for each respondent. All the interview calls initiated well and ended
successfully without any network interference or physical interruptions.
I asked each participant all questions on the interview document (see Appendix B)
and sometimes asked follow-up questions to clarify information or for in-depth
information during interviewing. All the participants separately turned down my request to
audio record the interview calls for privacy reasons. I spent about 40 minutes asking
interview questions and taking interview notes on each call. After the interview, I read the
responses provided to each respondent to confirm or modify their answers to reflect what
they really wanted to say. This member checking process was completed within 30
minutes for each participant. All the participants did the member checking for credible and
accurate data. I also used peer debriefing technique to check my own bias in data coding
and analysis. I converted the interview notes into a MS Word document for each
participant. I stored the data on electronic files in Dropbox (cloud) with backup on an
encrypted flash drive, which I stored in a locked cabinet. Some information about the

50
causes of undocumented immigration from Mexico to the United States was obtained
from the website of DHS. However, I could not assess or obtain information on the
challenges of healthcare accessibility in Mexico on the website of Mexico Health
Department. This was the only variation in the data collection plan outlined in Chapter 3.
Data Analysis
I used ATLAS.ti software to code and analyze the data. After I completed
interviews and member checking to confirm participants’ responses and make corrections,
I converted the interview notes of each participant into MS Word document. I applied the
iterative process (Pietkiewicz & Smith, 2014), which required that I and thoroughly and
closely read and reread the transcript, highlighting experiences of the participants on
challenges of healthcare in Mexico to influence to immigrate to the United States for
healthcare access. As I listened to participants and asked follow-up questions during the
interviews in addition to reading the interview notes I found some statements and words
that helped me to understand the experiences of the participants about the role of
healthcare in Mexico in undocumented immigration to the United States.
Using the ATLAS.ti software, I uploaded each participant’s responses and the DHS
website’s article on undocumented immigration in a form of word document and assigned
codes to the statements related to the research question. For the first cycle coding, I used
descriptive coding method. Here I described each participant’s response with simply
words and statements. For the second cycle coding, I used concept coding where I
assigned concepts to the descriptive statements in the first cycle coding. Finally, I looked
for patterns and similar concepts in participants responses I and grouped those patterns
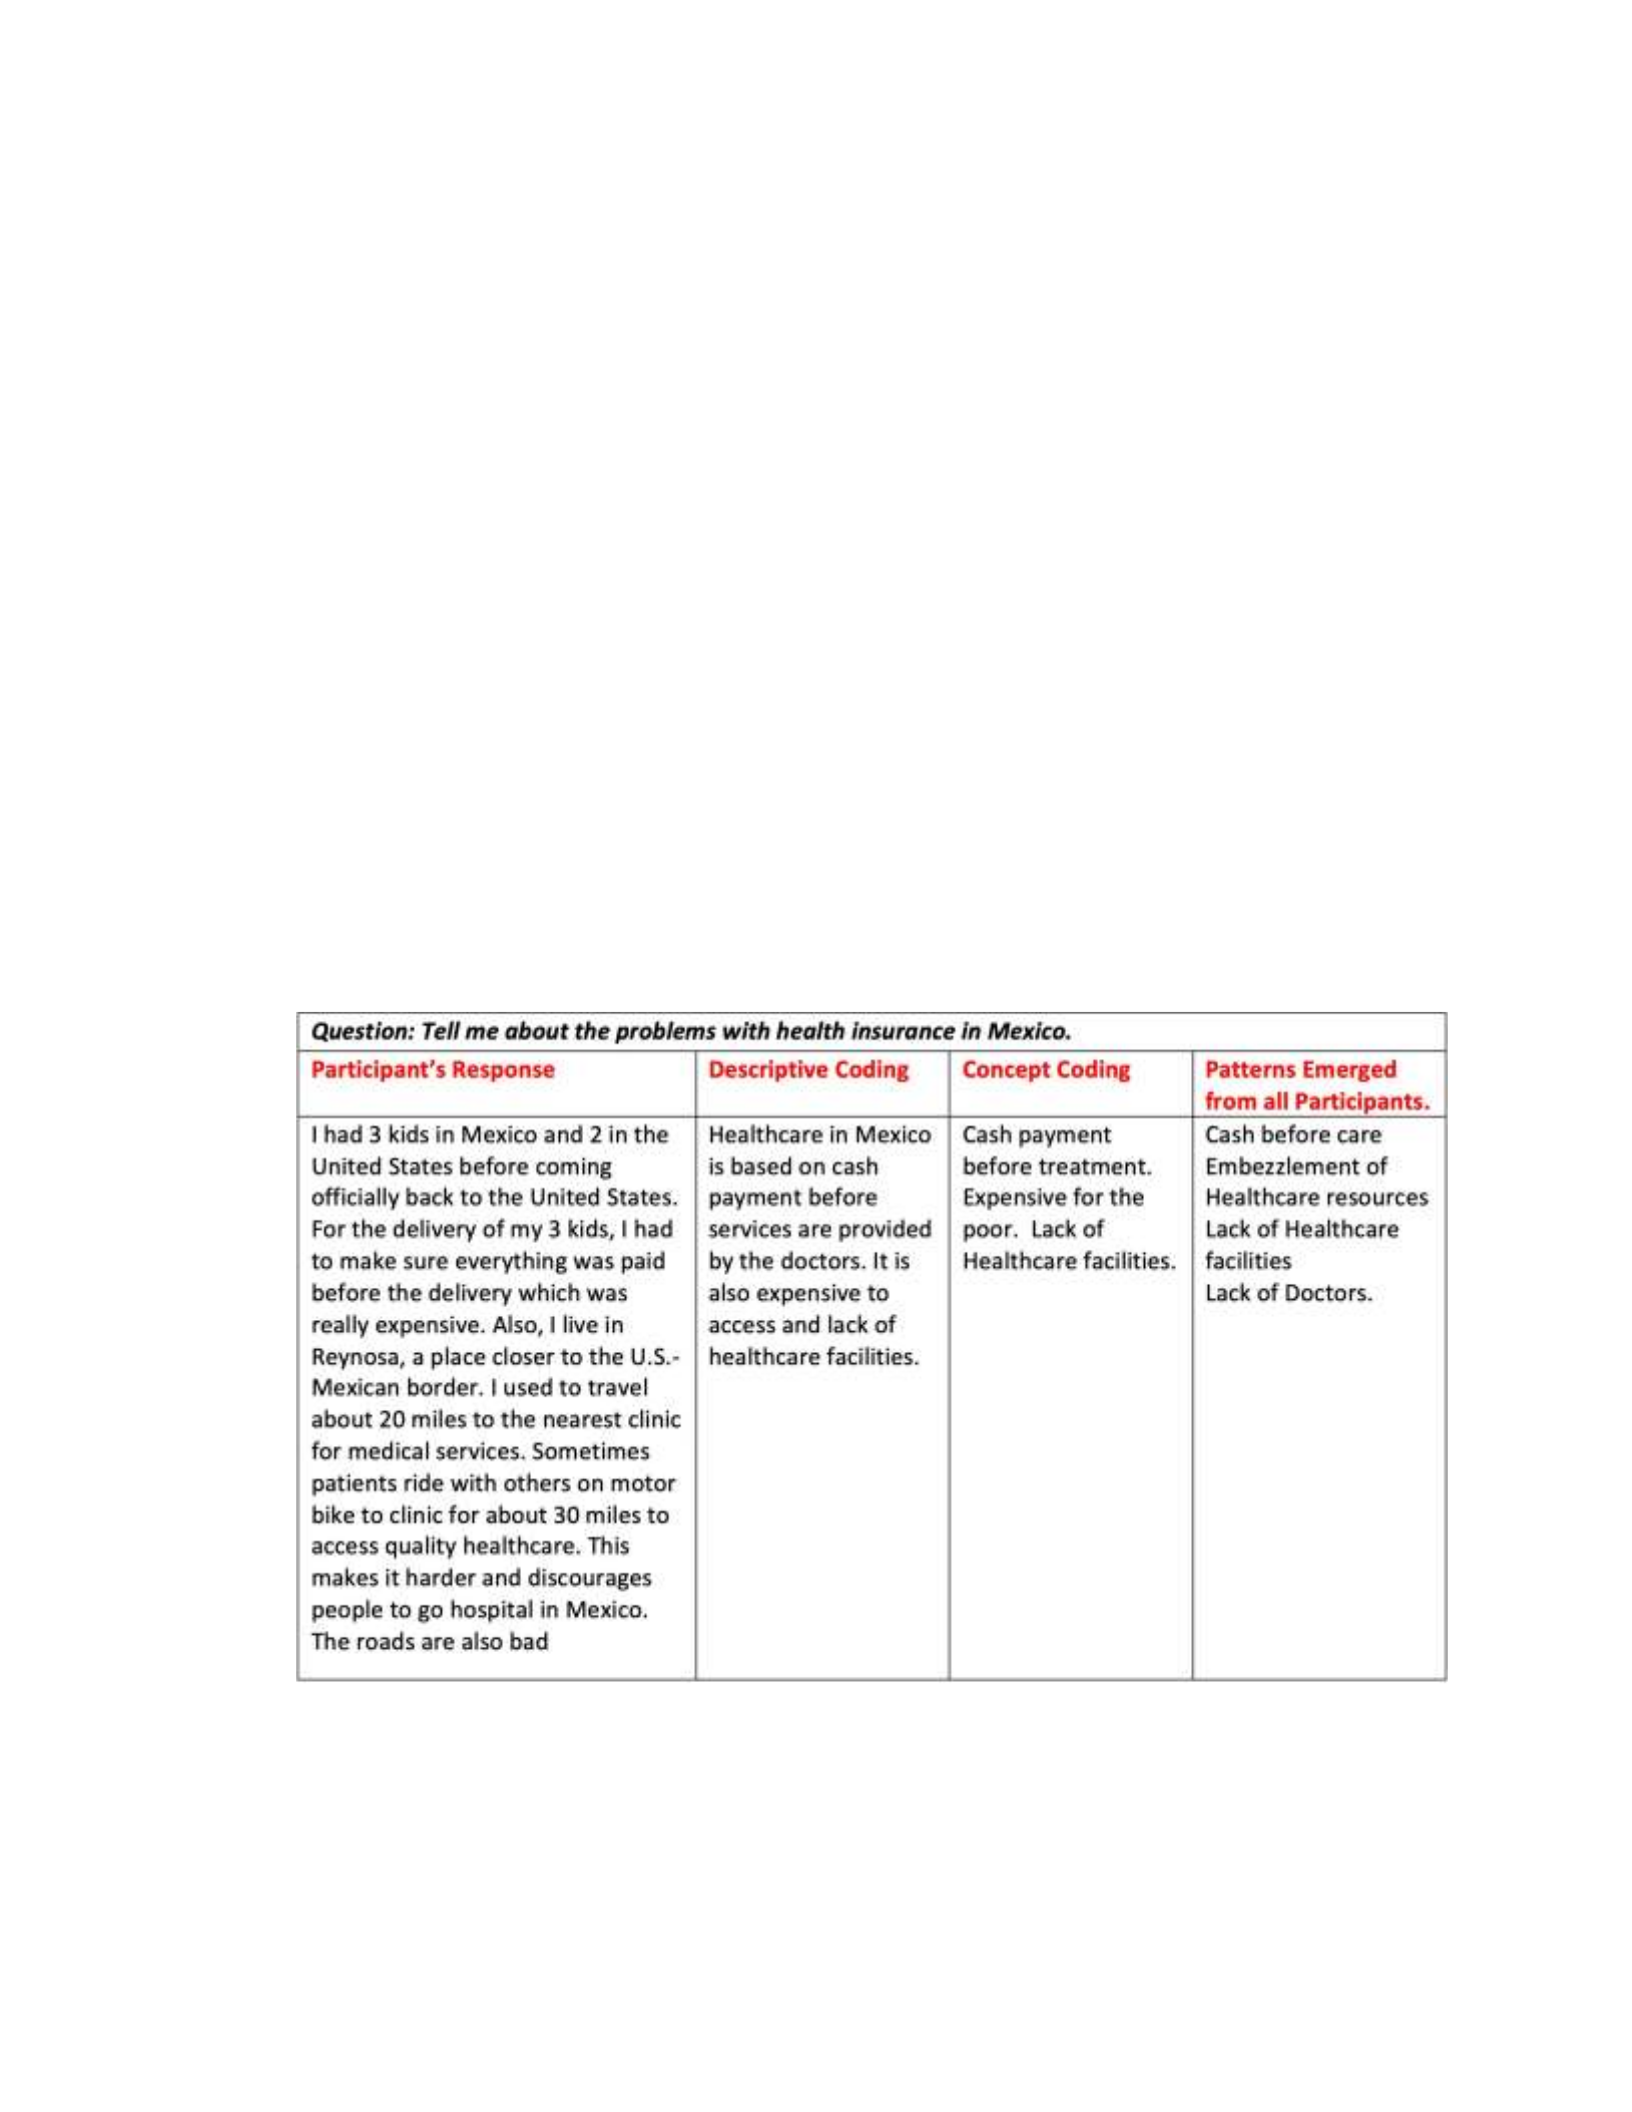
51
into themes. The Figure 3 below illustrated and summarized the coding process I used.
Some of the themes I generated relating to challenges of healthcare in Mexico (push
factors) included: (a) paying cash before receiving medical services, (b) corruption, (c)
lack of hospitals or clinics at the rural areas, and (d) lack of personnel or doctors.
Themes I generated on the pull factors of health insurance in the United States included:
(a) cheaper price, (b) perception of free medical services in emergencies, and (c) quality
healthcare services.
Figure 3
Coding Process
Note. The figure is an output of ATLAS.ti used in the coding. It illustrates the processes
followed. This process was repeated for each participant’s responses to generate the
themes.

52
I noted discrepant views or cases in the data coding and analysis. Patton (2015)
explained that data discrepancy strengthens and shows the in-depth nature of data
patterns. I used the discrepant data to understand and validate different reasons people
have to immigrate to the United States. I compared the discrepant data to the main data
and realized that the discrepant data described availability of jobs as the primary driver of
immigration to the United States. This reason opens the gate for more research to
appreciate and understand the overall picture of immigration.
Evidence of Trustworthiness
To achieve data credibility, I followed the plan I outlined in Chapter 3. To ensure
the data represent the actual view of the research participants, I used a member checking
technique to make sure I read each participant’s answers to them. This process provided
an opportunity for me to make corrections for the data to be credible and reflect what the
participants really wanted to say. I also used triangulation method by comparing data from
the interviews to information obtained from the website of DHS about reasons Mexicans
immigrate to the United States. I also thoroughly compared data of each participant to
ensure consistency and accuracy.
To achieve data transferability, I employed phenomenological research approach
and semistructured interviews. This method allowed the participants to provide in-depth
information and thick descriptions of their experience about the role of health care in
Mexico in undocumented immigration to the United States. According to Shenton (2004)
and Patton (2015) phenomenological study and semistructured interviews allow the
researcher to obtain detailed information to achieve data replicability and generalizability.

53
I also used a convenient purposive sampling strategy to select participants who have more
information about the topic. This helped me to achieve data transferability and
applicability of the findings.
I followed the plan explained in Chapter 3 to ensure data dependability. To ensure
consistency and reliability of my research findings I consulted my committee chair and
committee member when developing the interview questions to make sure all the
questions are realistic, aligned with the research question, and consistent with each other
(see Appendix B). Finally, because I used semistructured interviews, I was able to ask the
participants follow up questions for clarity and more information to make sure my
findings are dependable and consistent.
To achieve data confirmability, I used peer debriefing technique. As I explained in
Chapter 3, I posted the announcement on Walden students’ dissertation groups on
Facebook for interested person. The person sent me a private message on Facebook
messenger accepting to debrief my findings. The process started when I completed
interviews and ended when I finished data analysis. The peer reviewer double checked
interview notes, codes, and interpretations to make sure they are free from my personal
bias. Moon et al. (2016) explained that for data to be considered reliable, the researcher
must provide a detailed description of the methods, procedures, and processes used in
drawing conclusions for potential replication by others. All these procedures are explained
in Chapter 3. I also used member checking technique and research reflexibility on my
personal beliefs and perception to be neutral and transparent in data collection and
analysis to maximize confirmability.

54
Results
My research question was: What are the lived experiences of formerly
undocumented Mexican immigrants living in Hidalgo County, Texas, regarding the role of
healthcare in their decision to migrate to the United States? I used semistructured
interviews to explore lived experiences of the research participants. The data were
organized in MS Word document. I used ATLAS.ti software, descriptive and concept
coding strategy to code the research data. The themes that merged relevant to the push
factors included: (a) paying cash before receiving medical services, (b) corruption, (c)
lack of healthcare facilities at the rural areas, and (d) lack of doctors. These problems as
push factors, forced some participants to leave Mexico. The other themes that were
generated relating to the pull factors of healthcare insurance in the United States are: (a)
cheaper health insurance for healthcare, (b) perceived free medical services in
emergencies, and (c) quality healthcare services. The pull factor themes motivated and
encouraged some of the participants to migrate to the United States to access quality
healthcare. The study’s push/pull factor themes and discrepant data are discussed in this
section.
Theme 1: Pay Cash before Receiving Medical Services
The study’s findings revealed that the role of healthcare in Mexico in
undocumented immigration to the United States is, that people in Mexico more at times
are required to pay upfront for medical services even though they are insured. Based on
the comments by the respondents to pay cash before seen by a physician limited access to
quality healthcare especially the poor. Five of the seven respondents shared their views.

55
For instance, Juan noted “in order to have health insurance in Mexico you need a job.
Health insurance in Mexico is all about money and no doctor will you see you without
money even when you have insurance.” He added, that in Mexico to have any medical
procedure done you need to have the money right there and then. You cannot have any
medical procedure done without the money.
Maria stated “I had 3 kids in Mexico and 2 in the United States before coming to
the United States. For the delivery of my 3 kids, I had to make sure everything was paid
before the delivery which was really expensive.” According to Perez, it is hard to obtain
health insurance in Mexico, even if you have insurance everything is expensive. Rosa
summarized her experience in Mexico about paying cash before a doctor attend to you.
She stated “sometimes my doctor would ask me to buy injections from pharmacy and
bring them to the hospital for injection or treatment. It was appalling and disgraceful.”
Finally, commenting on the challenges of health insurance in Mexico, Kiara explained that
“in Mexico my insurance really didn’t cover anything, I had to pay everything upfront
even for the deliveries of my babies. I was always scared of needing emergency insurance
due to the money.” She expressed her view that physicians or nurses in Mexico have
prioritized money over human life and welfare.
Theme 2: Corruption and Embezzlement of Public Funds or Resources
All the 7 participants described how corruption and embezzlement of public
resources made it difficult for healthcare access in Mexico. John felt that many people in
Mexico have no access to healthcare because some politicians and public administrators
used public funds meant for expanding healthcare access for personal gains. He stated

56
“politicians and administrators in Mexico are corrupt to the core. The empty public coffers
for personal gains to the detriment of the poor to access quality healthcare.” Juan asserted
that corruption is the root cause of ineffective health insurance system. He narrated “my
friend used to tell me how some administrators in the Health Ministry in Mexico always
channel public funds meant to help the vulnerable to access healthcare for personal
benefits.” He described the situation as a “curse.” Maria who shared similar view with
Juan on corruption further explained that “everything is already planned out about making
it difficult for the poor to always suffer and the rich corrupt politicians continue to be
rich.” She felt the situation is unfair and disgusting.
Perez was emotional in describing the impact of corruption on healthcare access.
He stated “in Mexico corruption is bad, I don’t like talking about it; it’s politics. I try to
not get involved in them.” Even though he was not interested in talking about corruption,
he described it as a “sin” against the public and vulnerable as it denied them basic right to
have access to quality health care. Expressing her experience Rosa explained that
corruption is the main challenge for the people to access health insurance as corruption
leads to inadequate funds to expand access to healthcare. Kiara noted “public
administrators in charge of managing public funds for public good are rather using the
funds to buy nice houses and luxury cars draining the coffers meant to help expand health
care to the people at the rural areas and pay physicians.” Juliana had a moment to reflect
on her experience on corruption as a problem of health insurance in Mexico. She said her
father one narrated to her how politicians in Mexico have been using state resources for
personal gains. She lamented “One of the biggest problems of insurance in Mexico is

57
corruption.” She defined corruption as a situation where a public official uses public
resources such a money to satisfy his/her parochial interest while the vulnerable continue
to suffer.
Theme 3: Lack of Healthcare Facilities at Rural Areas
Four out of seven participants mentioned lack of healthcare facilities in rural areas
as one of the challenges of healthcare access in Mexico. Maria stated “I live in Reynosa, a
place closer to the U.S.-Mexican border. I used to travel about 20 miles to the nearest
clinic for medical services. Sometimes patients ride with others on motor bike to clinic for
about 30 miles to access quality healthcare. This makes it harder and discourages people
to go hospital in Mexico.” She added that some roads to certain clinics are nonmotorable.
According to Perez, inadequate number of health facilities leads traveling long
distances to access healthcare discourages some people to go to hospitals to seek
treatment. He stated, “healthcare facilities are congested in urban areas or cities, but many
rural areas lack clinics and hospitals and even roads leading to the few healthcare facilities
in the rural areas are deplorable.” He explained further that nurses and physicians do not
want to station at rural areas to provide quality healthcare to people who need as every
nurse and physician want to work in cities. These challenges increase waiting time to see a
nurse or doctor. Perez narrated that 50 years ago he visited a clinic in and waited a long 3
hours in a line to see a nurse. Finally, he and other 3 patients had to go back home without
seeing any nurse or attended to.
At Tamaulipas, closer to the Mexican-U.S. border, Juan explained that
unavailability of healthcare facilities such as clinics and hospitals denied some people to

58
access healthcare. He said he used to traveled long distance for about 3 hours on motor
bike to the nearest hospital to seek treatment. Juan posed an important question in
explaining his answer. He stated, “imagine what happens to patients who lived in my area
but who do not have motor bikes or cars to travel to the nearest hospital?”. Finally, in
addressing the question concerning challenges of healthcare access in Mexico, Juliana
explained that she used to travel about 6 miles on foot to the nearest hospital to access
healthcare. She stated “I went through hell” because of inadequate number of hospitals
and clinics in Mexico and lack of means or transportation to go to the clinic or hospitals.
Theme 4: Lack of Doctors
In explaining challenges of healthcare access, three out of seven participants
narrated their experience about lack or shortage of healthcare personnel affected their
access to healthcare in Mexico. In accounting her experience, Kiara stated “not having
enough doctors and nurses at hospitals and clinics is another problem making it harder on
people to access healthcare in Mexico. This results in long hours to see physicians and
nurses when you visit a facility. I remember on about three instances I had to wait in line
for more than 2 hours to see a doctor. It was terrible.”
Juliana explained that healthcare access is essential but lack of nurses and
physicians in Mexico has denied many people to access quality healthcare. She stated that
during the time she was diagnosed with hepatitis B she would go to a public hospital for
checkup and the doctor would not show up or she could wait for about 3 hours, because
the doctor had private hospital to attend to patients in that hospital. According to Juliana it

59
is because of lack of doctors in public healthcare facilities that made her experienced what
she explained, and it is a challenge for accessing quality healthcare in Mexico.
Finally, Rosa also shared her experience about lack of doctors in public hospitals
as a problem of healthcare access in Mexico. She narrated “before I immigrated to the
United States, there was doctor in my community’s government hospital in Mexico. The
hospital only had nurses who are not trained to do surgeries and other complicated
medical conditions.” She explained further that lack of specialists in hospitals discourages
people to visit hospitals when they are sick and that complicates medical conditions
needing more attention and money for treatment.
The themes that were generated as pull factors of immigration to the United States
from Mexico for healthcare access are discussed below: it was a probing question put
before all participants.
Theme 1: Perceived Free Access to Healthcare in Emergencies
During the interviewing four out of seven participants explained their experience
as undocumented immigrants about free access to healthcare in emergencies is a pull
factor for immigration to the United States from Mexico. Kiara accounted that: I knew
as an undocumented I could go by the hospital anytime and I would be given healthcare
access without insurance if my medical condition is critical. And
I would not pay anything to see a doctor in emergency which is not possible in
Mexico.
She added “If I’m honest I feel safer in the United States than Mexico.” She also added:
My husband had a lot of health problems and while living in Mexico we couldn’t

60
afford anything. We decided to move to the United States because of him, he had
more access to healthcare here through the help of some organizations. He passed
away about 3 years ago due to a work accident, he wasn’t denied healthcare access
due to no insurance. He was even transported via a helicopter to another city end
up to this date we have not been charged a single dime for it.
Maria also said
When I came to the United States before I become legal permanent resident, I had
2 surgeries as emergency and did not pay nothing. I also had my two daughters
here; I wasn’t expected to pay anything for them as well. On the contrary I was
given health insurance and for my baby while I was pregnant. Both of my kids had
access to free Health insurance which was a great benefit. In the United States the
healthcare services are more quality than services in Mexico. They have better
medicines and doctors and equipment.
Rosa also explained that when she arrived in the United States from Mexico:
I was able to see that in the United States health insurance access was way easier. I
did not have health insurance here yet due to being illegal, but I went the hospital
anytime and I would be given healthcare access without insurance in life
threatening situations. And I would not pay anything to see a doctor under
emergency which is not possible in Mexico.
Finally, during the interview process Juan also shared “I moved to the USA because of job
and healthcare access. Health insurance in the United States is more accessible. If I need
to go to the hospital, I don’t have to worry about having to pay before being seeing a

61
doctor. I was admitted to emergency room when I had car accident. I did not pay any
money before I was attended to. There is quality healthcare.”
Theme 2: Cheaper Health Insurance for Healthcare
Three of the participants explained that undocumented immigrants in the United
States buy health insurance at cheaper rates compared to documented immigrants and
citizens. According to Maria, it is not expensive for undocumented to buy health insurance
as some non-profit organizations help undocumented to acquire insurance. She noted
“many healthcare centers here funded by the federal government offered health insurance
at cheaper rates to the poor including the undocumented immigrants. After my surgeries as
an undocumented I bought health insurance at rate of $40 a month at Hidalgo Health
Center which is more expensive for documented immigrants and citizens who work.”
Juan narrated that accessing healthcare is cheaper for undocumented immigrants in
the United. She stated “there are independent charity organizations like Kaiser
Permanente Bridge Program which made me to apply for low-cost medical services. You
don’t need a social security number to apply. I applied and was approved. I paid $35 a
month just for primary healthcare services”. The enrollment helped me a lot to access
healthcare at lower prices when I was undocumented.
Finally, in the interview Rosa shared her experience that as an undocumented,
accessing health care insurance is cheaper and easier for her. She explained that some
health facilities and hospitals receiving some federal funding provide health insurance at
cheaper rate to poor person including undocumented immigrants who cannot afford to pay
for higher rates. She continued “for instance when I arrived in the country as

62
undocumented the Catholic Church, I attend, provided me the necessary financial help to
acquire health insurance and later I bought insurance at cheaper rate of $40 a month until I
become documented.” Healthcare services were also provided by newly trained doctors at
San Antonino hospital at lower cost or free to poor people and undocumented immigrants
according to Rosa.
Theme 3: Quality Healthcare Services
All seven participants agreed and stated that there are better quality healthcare
services in the United States than in Mexico. However, four out of seven participants
admitted that the availability of the quality healthcare services in the United States
influenced their decisions to relocate to the United States. Maria is noted to have explain
that there are better doctors, machines and medicines in the United States compared to
Mexico and everyone is interested in accessing what is better. She added that she had two
surgeries as an undocumented immigrant in the United States and had seen better
equipment, doctors, and medicines in the whole process. According to her Mexican
hospitals and healthcare facilities lack some of these equipment, specialized doctors, and
medicines.
Kiara also indicated that quality of healthcare services is better in the United
Sates than Mexico because of the technology gap between Mexico and United States.
Rosa also mentioned that she migrated to the United States because she believed there are
better doctors and medicines in the United States and that is proven when she visited
hospital for the first time as undocumented immigrant. She said, “the doctors were nice
and kind to me and would speak soft words to me and give me hope all the time but in

63
Mexico sometimes doctors would be treating me like trash and don’t care about I feel”.
Finally, Juan also mentioned that she moved to the United States because of healthcare
access. She explained that United States has more sophisticated and modern medical
machines and tools and more specialized doctors than Mexico. She narrated “I feel safer
and confident in the quality of healthcare I received in the U.S. than in Mexico even
though sometimes it is more costly than Mexico. However, in all U.S. is better than
Mexico in terms of quality of healthcare access. Figure 4 below summarized themes of
the research findings by illustrating reasons some of the participants migrated from
Mexico to the United States.
Figure 4
Push/Pull Factors of Migration
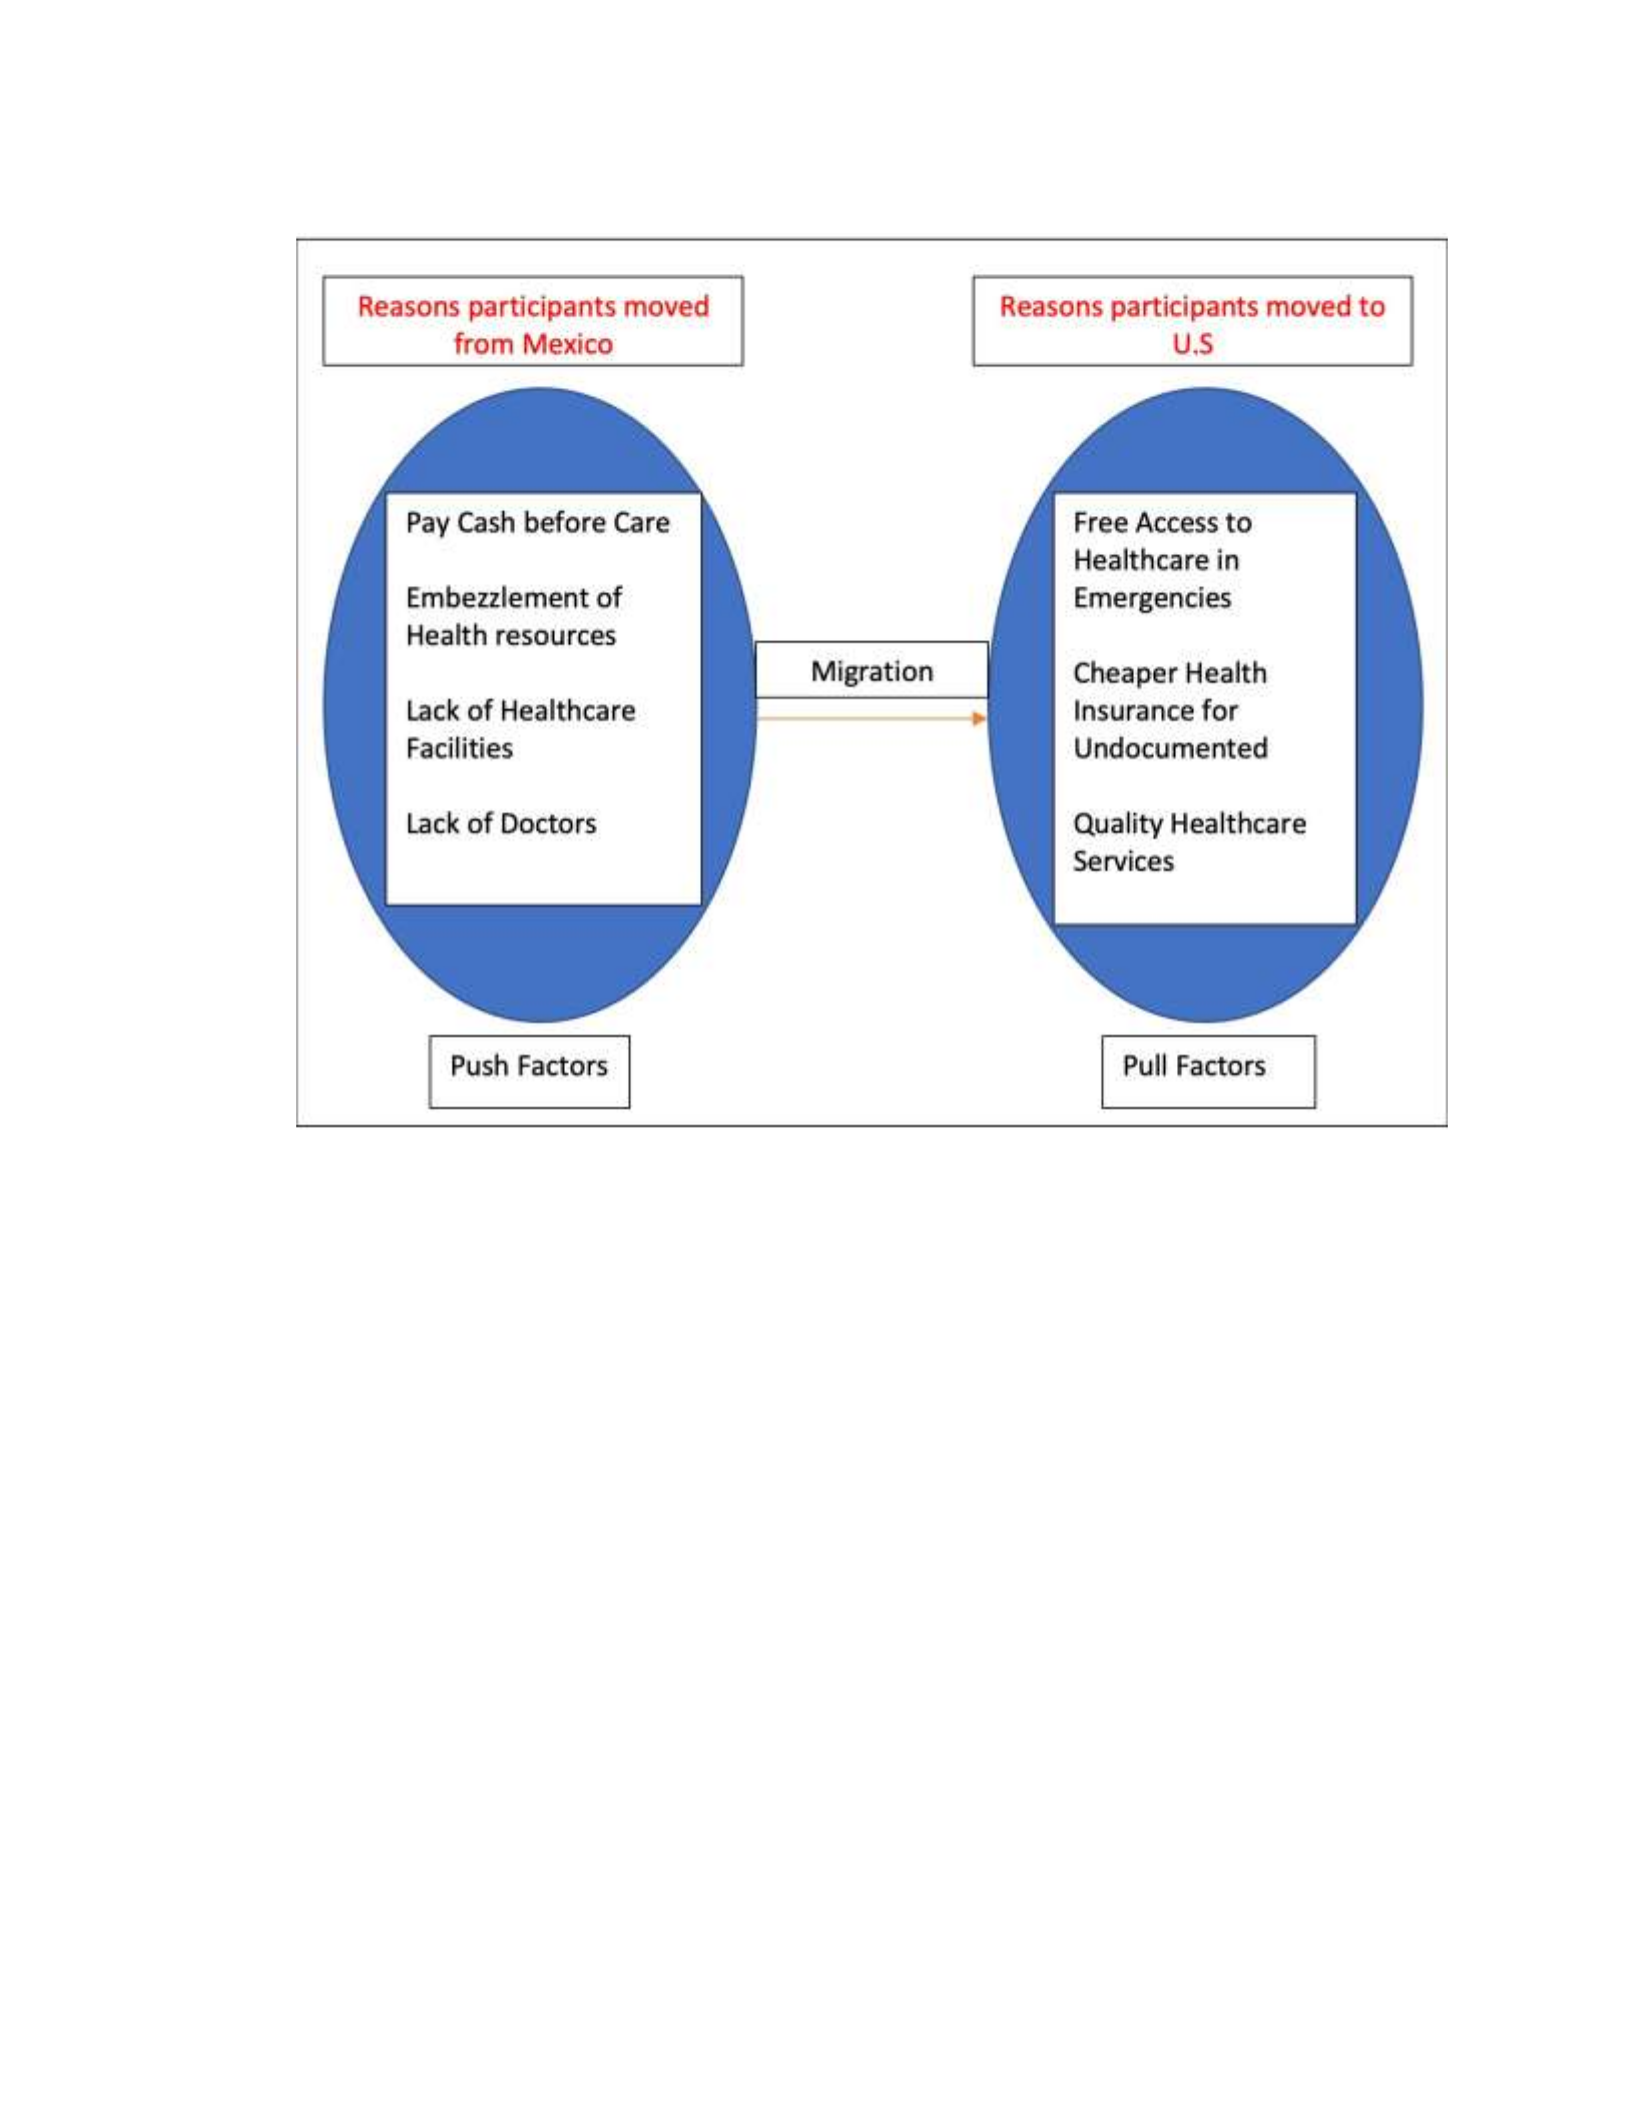
64
Note. The figure illustrates reasons some of the participants migrated from Mexico (push
factors) and reasons they migrated to the United States (pull factors) for healthcare access.
Discrepant Data
Discrepant data is normal in research studies and proves quality of data (Miles et
al. (2014). During the interviews, three out of seven participants explained that they
moved to the United States because of jobs opportunities and reuniting with families, but
not because of healthcare access. According to Perez “I immigrated to the United States
because of my family”. Also, John in answering one of the follow-up questions about why
he migrated to the United States said the decision to migrate was family decision and they
moved here because of jobs availability. He answered “No, I would not but healthcare

65
insurance is better here. We came here because of availability of jobs.” Finally, Juliana
also stated that she migrated to the United States to find better job, earn good income to
take care of the family. According to the U.S. DHS (n.d.) the primary driver of
immigration to the United States is the availability of jobs opportunities and family
reunion.
Summary
The main research question is, what are the lived experiences of formerly
undocumented Mexican immigrants living in Hidalgo County, Texas, regarding the role of
healthcare in their decision to migrate to the United States? The main purpose of the
research question is for me to explore the lived experiences of participants about the
problems of healthcare access in Mexico motivating them to immigrate to the United
States to access quality healthcare. To explore those experiences, I composed a
semistructured interview script, conducted interviews, and analyzed the data to discover
emerging themes.
In responding to the question about problems with health insurance in Mexico,
participants mentioned embezzlement of public health resources for personal gains, lack
of healthcare facilities at the rural areas, lack of doctors, and pay before care as major
challenges. And in responding to the question about the healthcare benefits in the United
State which could serve as pull factors, the participants mentioned the perception of free
healthcare access in emergencies, cheaper health insurance for undocumented immigrants,
and quality healthcare services. He explained why people moved from an area or location
to different place. The results from the analysis explained healthcare reasons some of the

66
participants migrated from Mexico to United States. However, the primary leading factors
for immigration to the United States are availability of jobs in the
United States and reuniting with families.
Chapter 5: Discussion, Conclusions, and Recommendation
Introduction
The study’s purpose was to understand the role of healthcare quality in Mexico in
undocumented immigration to the United States. I used a phenomenological approach to
explore detailed and in-depth information from the research participants on how
challenges or problems of health insurance in Mexico could encourage some Mexicans to
cross to the United States to benefit from a free or lower cost of health care. My
conceptual framework is situated on Lee’s push/pull theory. The study’s focus was to
collect data from formerly undocumented immigrant from Mexico to understand
healthcare access challenges in Mexico that motivated them to enter United States as
undocumented immigrants.
The study’s key findings about challenges of healthcare access in Mexico include
embezzlement public health resources, payment before treatment, lack of healthcare
facilities at the rural areas, and lack of doctors in public hospitals. The key findings about
healthcare reasons which motivated some participants to migrated include a perception of
free access to healthcare in emergencies, cheaper health insurance for undocumented
compared to documented due to charity and other U.S. government funded programs, and
quality healthcare services. The key findings align with Lee’s push/pull theoretical
framework.

67
Interpretation of the Findings
The main research question is what are the lived experiences of formerly
undocumented Mexican immigrants living in Hidalgo County, Texas, regarding the role of
healthcare in their decision to migrate to the United States? I used two main interview
questions to explore the research question. One main interview question was focused to
explore problems of healthcare access in Mexico. The other question centered on the
benefits of healthcare in the United States that motivate undocumented immigrants to
immigrate to the United States from Mexico. Interpretations of the findings for these
questions and the literature reviewed in Chapter 2 are discussed below.
First, most of the research participants (5 of 7) stated that payment in cash before
receiving medical services is a challenge to healthcare access in Mexico especially among
the poor. The literature reviewed in Chapter 2 about healthcare access in Mexico
confirmed this finding. Martinez-Martinez and Rodriguez-Brito (2020) stated that Mexico
has one of the highest out-of-pocket healthcare expenses among the countries belonging to
the Organization for Economic Co-operation and Development and some doctors
requiring patients to make payments before being attended to. This makes it harder for the
poor and vulnerable to access healthcare in Mexico. To support this Pelcastre-Villauerte et
al. (2017), mentioned that in Mexico, 73% of the population live below poverty and face
challenges to get insured or pay their medical bills. Also, all the participants have
identified corruption and embezzlement of public resources as another problem for
providing quality healthcare for people in Mexico. This is confirmed in the literature
reviewed as Hone and Gómez-Dantés (2019), Rivera-Hernández et al. (2019), and Sosa

68
and Sosa-Rubi (2016) contended that presence of corruption and mismanagement of
public resources in Mexico is a key challenge to provide and expand healthcare access to
the people.
Additionally, the findings revealed that lack of healthcare facilities in rural areas in
Mexico makes it difficult for the people living in these areas to access quality healthcare.
Most of the participants shared their long travel experiences to find hospital or clinic. The
lack of healthcare facilities in rural areas is confirmed by the literature reviewed.
According to Hone and Gómez-Dantés (2019), Rivera-Hernández et al. (2019), and Sosa
and Sosa-Rubi (2016) lack of healthcare facilities in the rural areas has denied many
people especially in rural areas to accessible quality healthcare in Mexico. Finally, on the
problems of healthcare access in Mexico, majority of the research respondents identified
lack of doctors in the public hospitals. Each of those participants explained how lack of
doctors affected them in Mexico. As reviewed in Chapter 2, Hone and Gómez-Dantés,
Rivera-Hernández et al., and Sosa and Sosa-Rubi collaborated on lack of healthcare
personnel and doctors as a challenge to addressing inequities of healthcare access in
Mexico.
To begin with, my study’s findings revealed that majority of the research
participants immigrated to the United States because they had a perception that they are
entitle to free healthcare services in emergencies, despite this fact being untrue for the
providers of those healthcare services. According to my findings, participants had
information and beliefs that during emergency situations doctors in U.S. hospitals and

69
clinics are required by the federal law to treat patients regardless of their background or
immigration status. This finding coincided with the literature reviewed. Kuruvilla and
Raghavan (2014) clearly stated that hospitals that receive federal funding in the United
States must screen and stabilize patients who need emergency care for free regardless of
their immigration status and ability to pay. Emergency care is backed by EMTALA, which
was first signed into law in 1986. Castaneda (2016) stated that in many large medical
schools, medical students provide free health care to the poor including undocumented
immigrants as part of their training rotations. However, according to Sawyer (2017), the
perceived “free” care is never free to the provider. American College of Emergency
Physicians (n.d.) added that emergency physicians on average provide $138,300 of
EMTALA charity care each year and incur on average $25,000 EMTALArelated-bad debt
in 2001 per the research conducted by American Medical Association (AMA) in May
2003. Further, the American Hospital Association (2021, February 28) has estimated that
approximately $660 billion dollars in the past 20 years has been spent in EMTALA and
other unfunded care resulting in upwards shifts of pricing to cover costs directly
impacting consumers and business alike.
The findings also revealed that healthcare insurance is cheaper for undocumented
immigrants in the United States. Some of respondents shared their experiences of
acquiring lower-cost health insurance from some community healthcare services and
nonprofit organizations. This information is confirmed by the literature in Chapter 2.
According to the literature some community health facilities, churches, and non-profit
organizations help undocumented immigrants to get health insurance at lower cost

70
(Artiga & Diaz, 2019; Castaneda, 2016; Flavin et al., 2018; Kuruvilla & Raghavan, 2014).
Also as already stated, in some larger medical schools’ medical students provide free
medical services to the vulnerable including undocumented immigrants (Castaneda,
2016).
Finally, some of the participants also mentioned that the healthcare services in the
United States are of higher quality than services provided in Mexico. They explained that
United States has better medical equipment and specialized doctors than Mexico. And this
has influenced their decision to move to the United States. This finding is not confirmed
by the literature reviewed.
By and large, these findings are aligned with the conceptual framework for this
study (Lee’s push/pull theory). Lee articulated that migration is caused by both push and
pull factors with intervening obstacles (Lee, 1966). The push factors according to the
findings are the challenges for healthcare access in Mexico. They are: (a) payments are
made before treatment, (b) corruption or embezzlement of public resources for personal
gains, (c) lack of healthcare facilities, and (d) lack of personnel or doctors in public
hospitals. The pull factors according to the findings are conditions in the United States
that promote access to quality healthcare to undocumented immigrants. They are: (a)
perceptions of free access to healthcare in emergencies, (b) cheaper health insurance for
undocumented immigrants, and (c) more quality healthcare services. The intervening
obstacles included hunger and fear of being shot or arrested.

71
Limitations of the Study
One of the study limitations is that majority of the interviews were not audio
recorded. This might have affected the quality of data collected, due to the difficulty
presented by listening to participants and taking notes simultaneously during interviews
(Ravitch & Carl, 2016; Rubin & Rubin, 2012). Secondly, I used a nonprobability
sampling technique to select the research participants. This technique, according to
Ravitch and Carl (2016), lacks randomness and enhances potential researcher. However,
Moustakas (1994) argued that the nonprobability technique can be used in qualitative
research because qualitative research focuses on discovering and providing in-depth
information on a topic to provide a better understanding but not how often something
happens. In addressing this, I used a nonprobability, convenient purposive sampling to
explore detailed and in-depth data. I also used triangulation, peer debriefing, and
bracketing strategies to check my personal bias to strengthen the credibility and
trustworthiness of the research findings. Finally, I used member checking technique to
double check and confirm answers participants provided to ensure the answers captured
were the correct answers participants wanted to provide to achieve data credibility.
Recommendations
There are two recommendations that emerged. The study was only conducted in
Hidalgo County, Texas. The study can be replicated in other neighboring counties and
states to study the overall impact healthcare benefits have on undocumented immigration
to the United States. According to the literature reviewed in Chapter 2, California is the
first state in the United States to provide state government-subsidized health benefits to

72
young undocumented immigrants (Allyn, 2019). This is an avenue for future research.
Another possible research area in the future is to widen scope of the study to include other
countries such as El Salvador, Cuba, East Africa, and West Africa as number of
immigrants in those areas keep increasing (Justice for Migrants, 2017 & Murtaza, 2020).
Implications
Finding ways to identify challenges for healthcare access in Mexico, the findings
will enlighten people about the role of healthcare in Mexico as a push for undocumented
immigration to the United Sates. The findings will also have positive implications for
social change in the field of public policy since it will add to our understanding of the
relationship between healthcare and immigration. It will also provide useful information
to the Hidalgo County local health department officials and United States Immigration
policy setters to better guide their debate and policies on healthcare policy. Also, the U.S.
Government needs to spend more time and resources to disabuse persons of the
information that emergency healthcare is “free”. The findings also revealed that the
primary factors leading of immigration to the United States are jobs availability and
reuniting with families and this information should help guide policies and debate on
immigration.
Conclusion
The study’s purpose was designed to understand the role of healthcare quality in
Mexico in undocumented immigration to the United States. The main research focused on
exploring the lived experiences of formerly undocumented Mexican immigrants living in
Hidalgo County, Texas, United States. A phenomenological approach was used. A

73
convenient non-probability sampling techniques was used to select all the research
participants. The conceptual framework was Lee’s push/pull theory of migration.
Based on the findings, majority of the research participants stated they moved to
the United States as undocumented immigrants to access quality healthcare. The research
findings are in line with Lee’s push factors of migration as the healthcare challenges in
Mexico served as the push factors. There are (a) payments are made before treatment, (b)
corruption or embezzlement of public resources for personal gains, (c) lack of healthcare
facilities, and (d) lack of personnel or doctors in public hospitals. The study’s findings on
Lee’s pull factors for the participants migration to the United States include (a) a
perception of free access to healthcare in emergencies, (b) cheaper health insurance for
undocumented immigrants, and (c) quality healthcare services. The implication of the
findings for social change is to enlighten us about the relationship between healthcare
access and migration and provide useful information for Hidalgo County local health
authorities and United States Immigration policy setters to better guide debate on public
healthcare policies. The U.S. government would be well served to spend time to clear
some misconception that emergency healthcare is “free”. Finally, the information that
availability of jobs and family reunion as primary pull factors of immigration to the
United Sates should be used by immigration legislators in the United States to help guide
debate on immigration policies.
Healthcare access in Mexico over a decade has faced some challenges. According
to Pelcastre-Villauerte et al. (2017), 73% of the population in Mexico live below the
poverty line of $10 a day and consequently, they are unable to purchase private health

74
insurance. The provision of healthcare services in Mexico can be acquired through public
or private insurance, but most of the services are provided under Popular Insurance,
known in Spanish as Seguro Popular (S.P.; Hone & Gómez-Dantés, 2019;
MartinezMartinez & Rodriguez, 2020; Sosa & Sosa-Rubi, 2016).
In May 2003, the government of Mexico established the S.P. to extend quality
healthcare insurance to the poor, under-insured, and uninsured, to address inequities in
quality healthcare access. Unfortunately, the program failed, and many people still lack
health insurance and quality health care services (Hone & Gómez-Dantés, 2019; Sosa &
Sosa-Rubi, 2016). Only 42.2% of the poor who lack permanent jobs are covered by the
S.P. health insurance in Mexico (Martinez-Martinez & Rodriguez, 2020).
The findings of my study will shed light and provide more information on the role of
healthcare in Mexico in undocumented immigration to the United States. The findings of
this study can have positive implications in the field of public policy, because it will add
to our understanding of the relationship between healthcare and immigration and provide
useful information to better guide the debate on healthcare policy. The findings of my
study will also reveal how healthcare access in the United States motivates some people
from Mexico to immigrate to the United States in an undocumented status to have access
to quality healthcare. This information will open a new door for further research on how
quality healthcare in the United States can cause undocumented immigration. In this
chapter, I provide an overview of the work by highlighting the background of the study,
the problem statement and purpose, and research questions. I also present the theoretical

75
foundation of the study, the nature of the study, and its limitations. Finally, I conclude the
chapter with a discussion of the potential significance of the study.
Background of the Study
Inés Ospina (2019), Macías-Rojas (2018), Orrenius and Zavodny (2019), and
Roberts (2017) explained that undocumented immigration had become a major political,
social, and economic problem in the United States over the decade. According to Heslin
(2018) and Hoekstra and Orozco-Aleman (2017), approximately 12 million
undocumented immigrants are living in the United States, making it difficult for the
government to track the population and implement social intervention policies.
Access to quality healthcare is a problem in Mexico. Pelcastre-Villauerte et al.
(2018), Guerra et al. (2018), Hone and Gómez-Dantés (2019), Martinez-Martinez and
Rodriguez (2020), Sosa and Sosa-Rubi (2016) explained that about 55% of the population
in Mexico lack access to quality healthcare insurance even after the implementation of the
S.P. program. According to Sosa and Sosa-Rubi and Hone and
Gómez-Dantés, healthcare access in Mexico increased because of the implementation of
S.P however, there remains several people who are uninsured or underinsured because of
lack of financial resources and effective management of the S.P. by the government. My
study will explore the role of healthcare in Mexico in undocumented immigration to the
United States. It will provide in-depth information on lived experiences of undocumented
immigrants to better understand the role of healthcare in undocumented immigration to
the United States. Also, this information can better guide debates on healthcare public
policies.

76
Problem Statement
In the United States, undocumented immigration has been a major social and
political problem (Robert, 2017). Historically, the long border between United States and
Mexico has been the focus of American government in curbing undocumented
immigration (Inés Ospina, 2019). Nearly 11 million undocumented immigrants are living
in the United States (Heslin, 2018; Hoekstra & Orozco-Aleman, 2017). According to
Passel and Cohn (2019), in 2017, there were 10.5 million undocumented immigrants in
the United States, including 4.9 million Mexicans (47 %), marking the first time that
undocumented immigrants from Mexico fell below half of the total undocumented
immigrants (Passel & Cohn, 2019). There are many reasons people immigrate to the
United States. According to Macías-Rojas (2018) and Robert (2017), the primary reasons
people immigrate to the United States include: employment, fleeing political persecution,
reuniting with family, and the desire to live in a free society.
Due to the social, political, and economic issues, such as an abundance of narcotic
drugs, pressure on social programs, and pressure on jobs associated with undocumented
immigration, Congress, in 1996, passed the Illegal Immigration Reform and Immigrant
Responsibility Act (IIRIRA) to reduce the undocumented immigration (Macías-Rojas,
2018). The probability rate of arrest and apprehension of undocumented immigrants has
increased from 40% in 2000 to 55% by 2015; approximately 304,000 undocumented
immigrants were apprehended along the U.S.-Mexican border in the 2017 fiscal year
(Orrenius & Zavodny, 2019). Another effect of undocumented immigration is that

77
American citizens are divided on the issue of undocumented immigration and the
divisions are along party lines (Robert, 2017).
The nature of health insurance in Mexico and its challenges, such as being
expensive, lack of quality healthcare services, and inaccessibility, have been recently
studied (Hone & Gómez-Dantés, 2019; Martinez-Martinez & Rodriguez-Brito, 2020;
Rivera-Hernández et al., 2019; Sosa & Sosa-Rubi, 2016). There is an existing body of
information on healthcare in Mexico, but that research does not significantly focus on
ineffective health insurance in Mexico and its relation to undocumented immigration in
the United States. This study will fill this gap by contributing to the body of information
needed to address the problem by providing an evidence-based approach to inform public
policy.
According to Pelcastre-Villauerte et al. (2017), in Mexico, 73% of the population
live below the poverty line and face challenges in purchasing private insurance. The
provision of healthcare services in Mexico can be acquired through public or private
insurance, but most of the services are provided under S.P. (Hone & Gómez-Dantés, 2019;
Martinez-Martinez & Rodriguez, 2020; Sosa & Sosa-Rubi, 2016). In May 2003, the
government of Mexico established the S.P. to extend quality healthcare insurance to the
poor, under-insured, and uninsured, to address inequities in quality healthcare access. This
was done through the 1983 amendment of Article 4 of the Mexican Constitution to
provide universal health care for every citizen (Guerra et al., 2018). Unfortunately, the
program failed, and many people still lack health insurance and quality health care
services (Hone & Gómez-Dantés, 2019; Sosa & Sosa-Rubi, 2016).

78
Only 42.2% of citizens that lack permanent jobs are covered by the S.P. health
insurance in Mexico (Martinez-Martinez & Rodriguez, 2020). The Mexican Institute of
Social Security (IMSS), which provides health insurance for only private companies’
employees, only covered 36.4% of eligible enrollees as many of them wanted to move to
S.P., which is relatively cheaper than the IMSS (Guerra et al., 2018; Martinez-Martinez &
Rodriguez-Brito, 2020). Although there exists evidence that S.P. has increased health
insurance coverage among the underserved, Mexico has one of the highest out-of-pocket
healthcare expenses among the countries belonging to the Organization for Economic Co-
operation and Development (Martinez-Martinez & Rodriguez-Brito, 2020). Despite the
improvement in healthcare insurance, inequities in healthcare provision and utilization
still exist because of lack of finance, personnel, and bureaucracy of the government (Hone
& Gómez-Dantés, 2019; Rivera-Hernández et al., 2019; Sosa & Sosa-
Rubi, 2016).
According to Artiga and Diaz (2019), Castaneda (2016), and Kuruvilla and
Raghavan (2014), even though undocumented immigrants in the United States are denied
healthcare from the Affordable Care Act (ACA) they may obtain low-cost care through
community health centers and hospitals that receive federal funding and are required to
screen and stabilize patients who need emergency care, regardless of their immigration
status. Emergency care is backed by the Emergency Medical Treatment and Active Labor
Act (EMTALA) which was first signed into law in 1986 (Kuruvilla & Raghavan, 2014).
Also, in many large medical schools, medical students provide free health care to
members of underserved communities, including undocumented immigrants, as part of

79
their training rotations (Castaneda, 2016). All these benefits may encourage some
Mexicans to embark on undocumented U.S. immigration to access free or lower-cost
quality health care for themselves and their children. Therefore, it is important to address
Mexico’s inaccessible health insurance to reduce the desire to participate in
undocumented immigration for the purpose to access free or lower-cost U.S. health care.
Purpose of the Study
The purpose of this qualitative study was to understand the role of healthcare
quality in Mexico in undocumented immigration to the United States. I used a
phenomenological approach to engage immigrants from Mexico to explore detailed and
in-depth information on how challenges or problems of health insurance in Mexico could
encourage some Mexicans to cross to the United States to benefit from a free or lower cost
of health care.
I recruited participants who were legal permanent residents and citizens of the
United States but focused on their healthcare access experiences both in Mexico and the
United States before they became legal residents. Smart phone interview was used to
obtain primary data from the participants using principles of confidentiality to protect
their welfare. The respondents were selected by using a convenient purposive sampling
strategy (see O’Sullivan et al., 2017; Ravitch & Carl, 2016). My study will include
persons residing in Hidalgo County, Texas.

80
Research Question
My study intended to answer the following principal research question: What are
the lived experiences of formerly undocumented Mexican immigrants living in Hidalgo
County, Texas, regarding the role of healthcare in their decision to migrate to the United
States?
Conceptual Framework
Lee’s (1996) push and pull theory of migration served as my conceptual
framework. According to Lee, social migration is premised on the push and pull factors
with intervening obstacles in the middle. For the push factors, Lee referred to undesirable
conditions such as poor healthcare, poverty, fear of political persecution, and famine that
force people to leave their homes for other places. The pull factors are conditions such as
good health, peace, good jobs, and prosperity that induce, motivate, and attract people to
places (Lee, 1996). While the push factors are associated with the place of origin, the pull
factors are related to the place of the destination. Lee stated that the decision of a person
to migrate is based on four factors: (a) push factors associated with the area of origin, (b)
pull factors associate with the area of destination, (c) intervening obstacles, and (d)
personal reasons (Lee, 1996). Lee’s push and pull theory of migration is suitable for this
study because it focuses on problems of healthcare insurance in Mexico encouraging
people to enter the United States as undocumented to have access to free or lower-cost
quality healthcare services.
The challenges of health insurance in Mexico may be seen as the push factors and
the free and lower cost of healthcare services for undocumented immigrants in the United
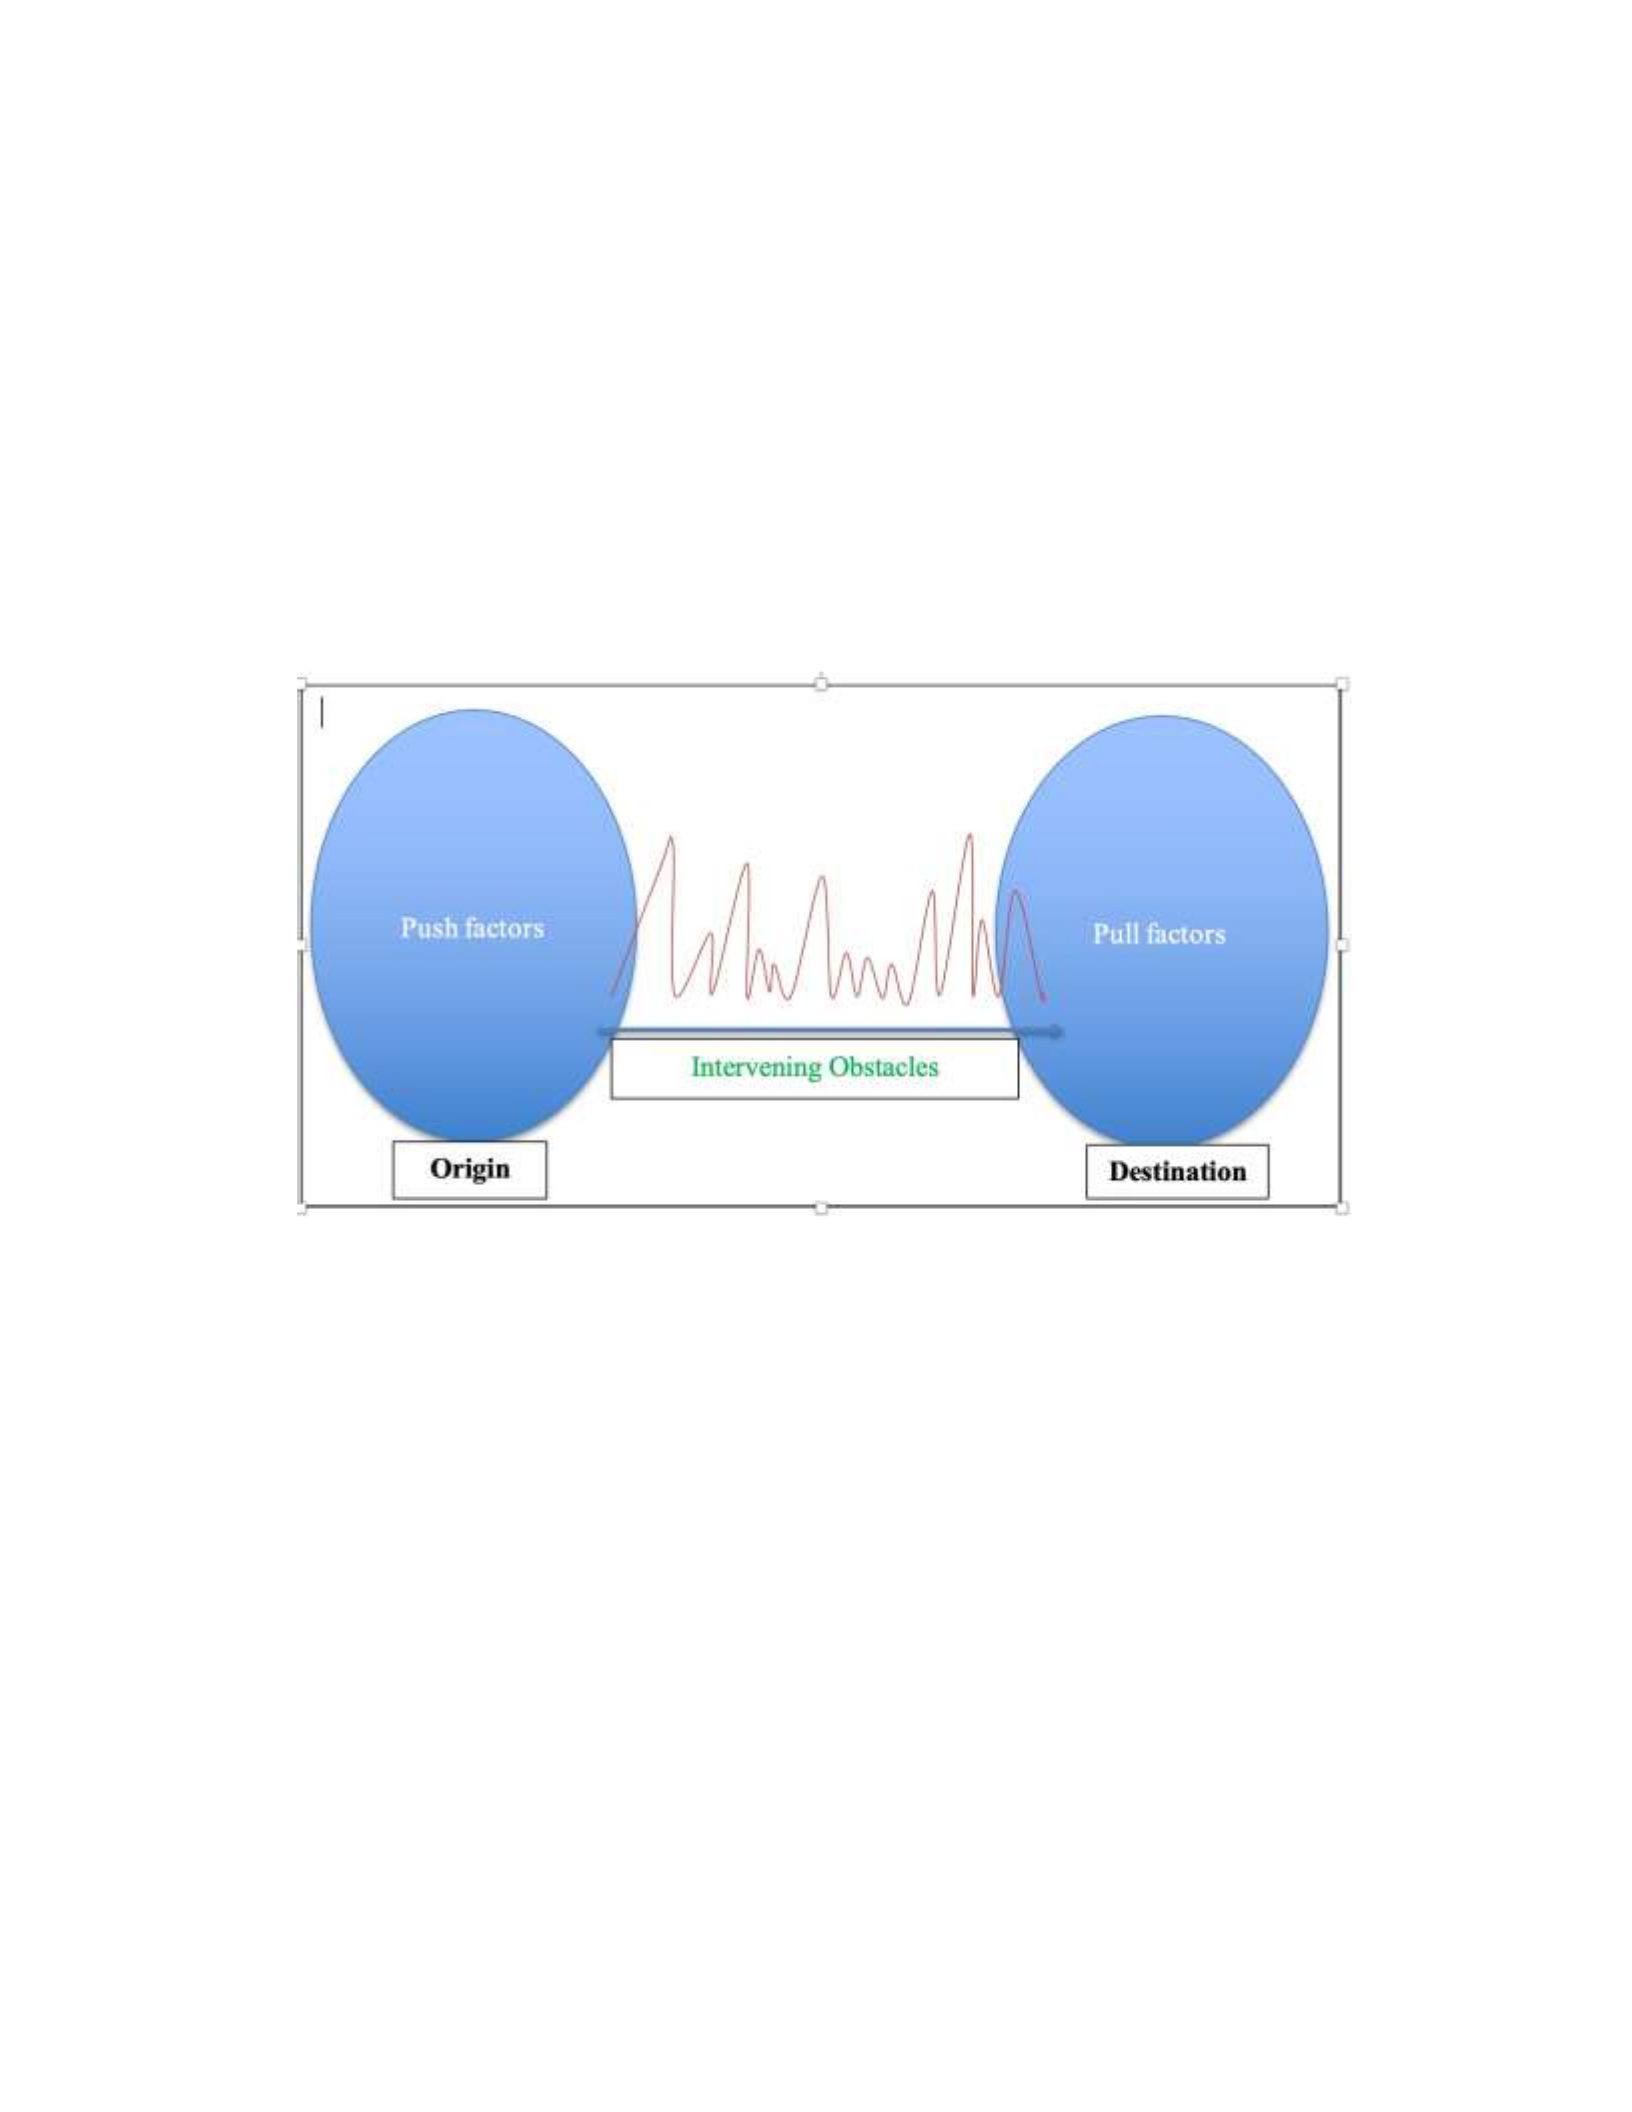
81
States through limited government programs may be seen as the pull factors as explained
in Lee’s theory. The intervening obstacles may refer to border security, distance, and
transportation challenges. The personal factors refer to the individual perceptions of both
the push and pull factors. Figure1presents the Lee’s model of migration.
Figure 1
Lee’s Model of Migration
Note. The model explains push factors as undesirable conditions at the original place that
discourages people to live there while pull factors at the destination motivate people to
move there. The intervening obstacles are conditions people experience or face during
movement from place of origin to destination.
Nature of the Study
My study used a phenomenological approach to examine the “lived experiences”
of migrants who experienced ineffective health insurance in Mexico, leading to
undocumented immigration to the United States. The study included the recruitment of
eligible participants in the United States.

82
Definitions
Affordable Care Act (ACA): It is officially knowns as Patient Protection and
Affordable Care Act, was passed into law in 2010 to expand the quality and affordable
healthcare to the uninsured and underinsured to promote healthcare accessibility
(Kuruvilla & Raghavan, 2014).
Emergency Medical Treatment and Labor Act (EMTALA): The Act was signed in
1986 stating that patients in emergency rooms must be treated regardless of their legal
status, insurance status, or ability to pay (Kuruvilla & Raghavan, 2014).
Immigration: It is the process through which a person or persons become
permanent residents or citizens of a different country (Parry, 2019).
Migration: It is the movement of people from one location to a particular location
because of push and pulls factors (Lee, 1996).
Push factors: These are issues that impel an individual to emigrate from his/her
country to a different country (Lee, 1996).
Pull factors: These are conditions that motivate a person to migrate to a different
location.
Undocumented immigrants: They are foreign-born individuals living in the United
States without authorization (Artiga & Diaz, 2019).
Assumptions
It is assumed that all research participants will participate willingly and honestly.
Another assumption is that all the participants have experienced challenges related to
health insurance in Mexico before becoming undocumented immigrants in the United

83
States. Participant confidentiality will be assured through the informed consent process
and interview design; therefore, it is assumed all participants will answer questions
truthfully. Finally, based on my background as an immigrant from Africa, I might be
biased in reporting some of the findings, but with my professional background, I should
be able to eliminate personal biases from the findings.
Scope and Delimitations
I recruited participants who are now legal permanent residents and citizens of the
United States but will focus on their healthcare access experiences both in Mexico and the
United States before they become legal residents. This study focused on in-depth
interviews of 7 participants. The research results may not reflect the experiences of all
undocumented immigrants, but it is assumed that it will represent a representative sample
of the target populations’ experiences. Hall (2010) interviewed five homeless individuals
for a phenomenological study on homelessness, and the results of the interviews indicated
that participants’ perceptions and experiences represent the entire homeless population in
the United States.
My study’s main challenge was language barriers. The research participants are
Hispanic, and some can only speak Spanish; a language I do not speak. Therefore, an
interpreter was used for participants who spoke Spanish for successful interviews. Also,
the time and location for interviews may pose an inconvenience, which may affect the
quality of the interviews. Another significant concern was the protection of the welfare of
the research participants. The confidentiality of the sensitive information provided by the
participants is paramount and must be abided by. However, divulging confidential

84
information of the participants through collection and analysis of data may harm the
participants in many ways, including economic, social, and psychological crises. As such,
all data will be reported using participant pseudonyms and aggregated themes apart from
some identity-protected statements that may help to illuminate individual and collective
experiences. My study’s purpose and objectives will be explained to the respondents and
their informed consent form will be obtained. Also, the SARS-CoV-2 (COVID-19)
pandemic may impact participant schedules and appointments, which may affect the
study’s overall timeline. The final limitation is the transferability and dependability of the
research findings as the study is qualitative and employs a non-probability sampling
strategy.
Limitations
I used a phenomenological approach to explore the lived experiences of Mexican
immigrants on the role of quality healthcare in their undocumented immigration to the
United States. One of the study limitations will be the difficulty in ensuring transferability
and dependability of study findings. Even though Lincoln and Guba (1985) and Shenton
(2004) explained strategies to achieve transferability and dependability (generalizability)
for qualitative research, both admitted it is difficult compared to quantitative research.
Secondly, I decided to use a nonprobability sampling technique to select participants. This
technique, according to Ravitch and Carl (2016), lacks randomness and enhances the
biases of the researcher. However, Moustakas (1994) argued that the nonprobability
technique can be used in qualitative research because qualitative research focuses on
discovering and providing in-depth information on a topic to provide a better

85
understanding but not how often something happens. In addressing this, I used a
nonprobability purposive sampling to explore my topic. I also used triangulation, member
checking, and peer debriefing strategies
Significance
My study focused on the role of healthcare in Mexico in undocumented
immigration to the United States. The findings will enlighten people about the role of
healthcare in undocumented immigration to the United Sates. The findings will also have
positive implications for social change in the field of public policy since it will add to our
understanding of the relationship between healthcare and immigration and provide useful
information to better guide the debate on healthcare policy.
Summary
In Chapter 1, I presented the background of the topic. I also detailed the problem
statement, purpose, and nature of the study in this chapter. I concluded Chapter 1 by
outlining the research questions, presented the conceptual framework, explained some
technical terms and research assumptions, outlined the scope and limitations, and finally
discussed the significance. Chapter 2 contains an in-depth literature review on
undocumented immigration, healthcare challenges in Mexico, and the conceptual
framework. Chapter 2 also presents a literature review on the research method and
approach. In Chapter 3, I presented information on the design of the research, role of the
researcher, selection of research participants, and instrumentation. This chapter also
covered procedures for data collection, data analysis plan, ethical procedures, and issues
of trustworthiness.

86
Chapter 2: Literature Review
Introduction
My study focused on exploring the research question: What are the lived
experiences of formerly undocumented Mexican immigrants living in Hidalgo County,
Texas, regarding the role of healthcare in their decision to migrate to the United States?
This chapter presents an approach for reviewing the literature. It includes an outline of the
historical, philosophical, and theoretical perception that entails immigration,
undocumented immigration, migration, and healthcare. The review of the literature starts
with an overview of the historical account of immigration, its effects, and policies put in
place to reduce undocumented immigration. The second section will present scholarly
literature relating to healthcare and its challenges in Mexico as well as healthcare for
undocumented immigrants in the United States. This chapter will also include a review of
the literature regarding the conceptual framework for the study. The final section will
address the literature review related to the approach and methodology.
Literature Search Strategy
For an intensive understanding and illustration of the theoretical and abstract
frameworks of the topic matter, the following databases were conjointly utilized: EBSCO,
ProQuest, ERIC, Google Scholar, and Healthcare Periodicals. I used the following
keywords in the search: immigration, undocumented immigration, undocumented
immigration, migration, healthcare insurance, migration theories, and push-pull theory. I
used relevant information from research articles, dissertations, books, seminars, and
organizations websites and the scope of publication year ranges from 1985 to 2020.

87
Historical Account of Immigration
Immigration is the process of moving to a new country to reside there permanently
(Connor, 2013; Parry, 2019). People who moved to a new country are called immigrants,
but these persons are called emigrants from the old country they moved away permanently
(Conner, 2016). Connor (2016) stated that the United Nations (UN) estimated there to be
232 million international migrants in the world, which is slightly more than 3% of the
world’s population. This percentage would be estimated to represent the world’s fifth-
most populous country if all the world’s migrants were living in a single country (Connor
& López, 2016).
According to Massey (1999), the modern history of international migration can be
divided into four periods: (a) the mercantile period, from 1500 to 1800 in which
immigration was dominated by Europe as a result of colonization and economic growth;
(b) the industrial period, which began from early 1800 to 1925 when more than 48 million
persons left Europe to the Americas and Oceania with a concentration of 85% to five
countries [Argentina, Australia, Canada, New Zealand, and the United States], with the
United States receiving 60 % of the 85% immigrants; (c) period of limited migration,
occurring in the 1930s where the receiving countries, most notably the United States, had
passed restrictive immigration laws because of the Great Depression; and (d) the period of
postindustrial migration in the 1960s during which immigration became a global issue
where sending countries like United Kingdom, France, Sweden, Italy, and Portugal as well
as the United States witnessed an overflow of immigrants from the developing countries
into their boarders.

88
Another history of mass movement of people occurred in Cuba in 1980 and 1994
(Martinez et al., 2015). In 1980, because of political and economic pressure on Cubans,
about 10,000 Cubans invaded the Peruvian Embassy seeking asylum and the Cubans
responded by opening port of Mariel to persons wishing to leave the country (Martinez et
al., 2015. They took the opportunity to decongest the prisons by expelling imprisoned
homosexuals and other prisoners. As a result of this mass immigration, more than 125,000
Cuban refugees arrived in Miami, Florida. Again, in August 1994, about 35,000
Cuban fled to Florida following the rafter crisis (Martinez et al., 2015).
Immigration in the United States
The United States has more immigrants than any other country in the world
(Budiman, 2020; Connor & López, 2016). Between 1880 and 1910 about, 17 million
European immigrants entered United States (Parry, 2019). More than 1 million
immigrants arrive in the United States each year (Budiman, 2020). As of 2015, the UN
stated that the immigrant population in the United States is about 46.6 million (Budiman,
2020; Connor & López, 2016). This represents 19% of the international immigrants. The
immigrant population in the United States is nearly four times that of the world’s next
largest immigrant destination – Germany, with an estimated immigrant population of 12
million (Budiman, 2020; Connor & López, 2016). According to Budiman (2020), in 2020
immigrants constituted approximately 13.7% of the U.S. population, 4.8 % in 1970, with
one of the largest migrations in the late 1800’s to fuel the U.S. industrial age. It is
estimated in 1890 that14.8% of the U.S. population, 9.2 million people, were immigrants.

89
Budiman (2020) further explained that only 77% of the immigrants in the United
States have followed legal processes and the rest are undocumented. It is important to
stress that since the formation of the federal Refugee Resettlement Program by the
Refugee Act in 1980, about 3 million refugees have admitted into the United States, more
than any other country in the world (Budiman, 2020; Connor & López, 2016).
Where Do U.S. Immigrants come from?
The United States of America is being described as the land of immigrants
according to Massey (1999), Parry (2019), and Robert (2017). Every year, about 1 million
immigrants arrive in the United States from all parts of the world; Mexico, China, India,
Philippines, El Salvador, Europe, Canada, Caribbean, Middle East, North Africa, and sub-
Saharan Africa (Budiman, 2020; Connor & López, 2016; Massey, 1999). For the
estimated 46.6 million immigrants of the United States, Mexico is the highest sending
country. In 2018, about 11.2 million (25%) immigrants living in the United States were
from Mexico, 6% each from China and India, 4% from the Philippines, 13% from Europe
and Canada, 10% from the Caribbean, 8% from Central America, 7% from South
America, 4% from the Middle East and North Africa, and finally 5% came from
subSaharan Africa (Budiman, 2020). In recent years new immigrant arrivals in the United
States have declined due to increasing immigration controls (Budiman, 2020; Orrenius &
Zavodny, 2019).
Undocumented Immigration
Most people have immigrated to the United States legally, but some have settled in
the country without permission. According to Martinez et al (2015), the term

90
undocumented immigrant is applicable under the following conditions: (a) legally entered
the country but remained in the country after their visa or permit expired; (b) received
negative remarks on their refugee or asylee application but remained in the country; (c)
experienced changes in their socioeconomic position but could not renew residence permit
but remained in the country; (d) used fraudulent documentation to enter the country; and
(e) unlawfully entered the country. Many of these people were desperate for a job, a better
life, or family reunification (Artiga & Diaz, 2019; Macías-Rojas, 2018;
Parry, 2019)
Robert (2017) explained that undocumented immigration has been considered one
of the major social, economic, and political problems in the United States. According to
Robert, polls conducted over the last 15 years revealed most Americans believe that U.S.
borders are not secured, and that the federal government could do more to reduce
undocumented immigration. As a result of this perception, border security has remained
the most controversial focal point of concern in the United States (Inés Ospina, 2019;
Roberts, 2017).
Nearly 11 million undocumented immigrants live in the United States (Heslin,
2018; Hoekstra & Orozco-Aleman, 2017). Budiman (2020) stated that from 1990, the
population of undocumented immigrants increased from 3.5 million to a high record of
12.2 million in 2007. However, by 2017, Passel and Cohn (2019) estimated the
undocumented immigrant population had decreased by 1.7 million, accounting for 10.5
million of which 4.9 million were estimated to be Mexicans. This constitutes 47% of
undocumented immigrants from Mexico in 2017, the first time the undocumented

91
immigrants from Mexico fell below half of the total undocumented immigrants (Passel &
Cohn, 2019). Budiman added that the 10.5 million undocumented immigrant population
constituted 3.2% of the overall U.S. population in 2017. Between 2007 and 2017 there
was a decrease of the Mexican undocumented immigrants by 2 million leading to an
overall decline of the undocumented immigrants from 12.2 million to 10.5 million in the
United States (Budiman, 2020; Passel & Cohn, 2019).
U.S. Public Perception of Undocumented immigrants
According to Gramlich (2019), a survey was conducted in June 2018 to obtain
opinions about immigrants in the United States. In this survey, only 45% of Americans
said most immigrants are in the country legally, but 35% incorrectly said that most of the
immigrants are in the country in an undocumented status. In another survey conducted
before the 2018 midterm elections among registered voters who planned to vote for
Republican and Democratic Parties, 75% of registered voters who planned to vote for the
Republican candidate said undocumented immigration was a serious problem in the
country against 19% among voters who planned to support Democratic candidate
(Gramlich, 2019). Gramlich also stated that 69% of Republicans agreed that expanding
the wall along the U.S Mexican border is a major restrictive measure to reduce
undocumented immigration, but 70% of Democrats indicated that measure would not be
effective in reducing undocumented immigration.
Baranowski (2012) and Krogstad (2020) stated that 74% of U.S. adults said they
favor granting permanent legal status to immigrants who came to the United States as
undocumented. Baranowski added that a survey was conducted among 686 participants

92
about perceptions of undocumented immigrants from Mexico. The findings revealed that
Latinos have more positive attitudes towards undocumented immigrants than White
Americans. Also, participants with higher education endorsed respect for undocumented
immigrants from Mexico more compared to participants with lower or without education
(Baranowski, 2012). Finally, participants who live within 200 miles of the U.S.- Mexican
border have less tolerant attitudes towards undocumented immigrants from Mexico than
participants who live far away from that region.
Effects of Immigration
There has an overwhelming pressure on healthcare infrastructure in the United
States and one of the causes is the rapid growth of undocumented immigrants (Muschek,
2015). Muschek added that the U.S. federal government spent about $29 billion to take
care of undocumented immigrants in the 2010 fiscal year. Out of this expenditure, $10.7
billion was spent on providing healthcare for undocumented immigrants (Muschek,
2015).
Undocumented immigration has led to an increase in population and an
overwhelming pressure on social welfare programs in the United States (Macías-Rojas,
2018; Muschek, 2015; Orrenius & Zavodny, 2019). Kerwin (2018) stated that, between
1997 and 2018, the budget of the U.S. DHS has increased from $1.935 billion to $21.1
billion in efforts to enhance border security and control undocumented entries. This
spending, including expenditure on the healthcare of immigrant children, drains the
federal coffers (Kerwin, 2018). According to Rueben and Gault (2017), when all the costs

93
of public goods are distributed to everyone in the United States, immigrant adults are
estimated to be more dependent on state and local budgets than native adults. There was a
$2,950 gap difference in budget impact between immigrants and individuals born in the
United States between 2011and 2013.
Borjas (2019) mentioned that from 1990 to 2014 the U.S. Gross Domestic Product
(GDP) would have been 15% less without the contribution and hard work of immigrants.
Borjas further explained that when the immigrants’ population increases by 1%, the
economy of the United States grows by 1.15%. This means that an increase in
immigration has been seen as a great contributor to the economic growth in the United
States. In 2016, foreign-born alone constitutes 16.6% of the labor force in the United
States contributing meaningfully to generating national wealth and output (Borjas, 2019).
According to Desilver (2019), in 2014 27.6 million immigrants were present in the U.S.
workforce of 161.4 million and out of the 27.6 million immigrants, 19.6 million came to
the United States legally; an estimated 8 million are undocumented (Desilver, 2019).
Immigration has been considered as source labor for the United States. In 2014, 33% of
farmworkers were immigrants, 45% of private households were immigrants, and 36% of
the textile and manufacturing industries employed immigrants (Desilver, 2019).
Gubernskaya and Dreby (2017) added that, generally, family-based immigration has a
positive impact on the economy of the United States compared to negative effects.
Healthcare and Undocumented immigrants
Flavin et al. (2018) mentioned that 52% of people in the United States believe that
expenditure on immigrants’ healthcare is a great burden on the economy and 67% of the

94
public hold the belief that undocumented immigrants should not qualify for social services
including healthcare. In the light of this, federal policies have been put in place to deny
undocumented immigrants’ access to public healthcare insurance, Medicare, and Medicaid
(Artiga & Diaz, 2019; Castaneda, 2016; Flavin et al., 2018; Kuruvilla & Raghavan, 2014).
The ACA, which was enacted in March 2010 by Congress to expand access to quality
healthcare, categorically denied undocumented immigrants from being covered (Artiga &
Diaz, 2019; Castaneda, 2016; Flavin et al., 2018; Kuruvilla & Raghavan, 2014). However,
undocumented immigrants may obtain low-cost health care through community health
centers, and hospitals that receive federal funding must screen and stabilize patients who
need emergency care for free regardless of their immigration status. Emergency care is
backed by the Emergency Medical Treatment and Active Labor
Act (EMTALA) which was first signed into law in 1986 (Kuruvilla & Raghavan, 2014).
Also, in many large medical schools, medical students provide free health care to the poor
including undocumented immigrants as part of their training rotations (Castaneda,
2016).
Allyn (2019) stated that California is the first U.S. state to provide state
government-subsidized health benefits to young undocumented immigrants. California,
since 2016, has allowed children less than 18 years to benefit from state taxpayer-backed
healthcare regardless of their immigration status (Allyn, 2019). Allyn added that the
lowincome undocumented immigrants aged 25 or younger are being covered by
California’s
Medicaid program.

95
Recent Efforts to Prevent and Reduce Undocumented Immigration
Due to the sociopolitical and economic issues, such as an abundance of narcotic
drugs, pressure on social programs, and pressure on jobs associated with undocumented
immigration, Congress, in 1996, passed the Illegal Immigration Reform and Immigrant
Responsibility Act (IIRIRA) to prevent or reduce the undocumented immigration
(Macías-Rojas, 2018). Orrenius and Zavodny (2019) stated that about 304, 000
undocumented migrants were arrested along the U.S. – Mexican border in 2017. This is
the lowest rate of apprehension since 1971. Robert (2017) corroborated that successful
undocumented entries in the United States have been reduced by 90% between 2005 to
2015 (from 2 million to 200,000) as a result of enhancing border security ranging from
added personnel to fencing to motion camera detection and the use of aerial surveillance.
The campaign of President Trump during the 2016 elections focused on the
negative effects of immigration included safety, narcotic abundance, rape, and job
security, and called for the need to extend the U.S.-Mexican southern border (Pierce,
2019). According to Pierce (2019), many enforcement measures were undertaken by the
Trump Administration to reduce undocumented immigration included if not all: (a)
National Guard deployment to the U.S. – Mexican border. As of March 2019, about
2,100 National Guards troops were still stationed at the border; (b) on April 6, 2018, the
Trump Administration declared a zero-tolerance policy on undocumented immigration
resulting in thousands of children being separated from their families; (c) active-duty
military deployment to the border in October 2018; and (d) increasing border patrol

96
staffing. In January 2017, President Trump ordered hiring 5,000 additional Border Patrol
officers and by the end of 2018, there were 21,370 officers authorized by Congress
(Pierce, 2019).
On April 29, 2019, the Associated Press reported that Acting Defense Secretary
Shanahan instructed that additional 230 troops be deployed to the southern U.S.-Mexican
border to help Customs and Border Protection (CBP) officers intensify efforts to secure
the border against undocumented entries. This deployment, approved by the Acting
Defense Secretary Shanahan, cost the federal government an estimated $7.4 million. This
money could have been used to address other social and economic challenges (Pierce,
2019).
Healthcare
Baltagi et al. (2017) investigated a relationship between healthcare expenditure
and individual income among 167 countries between 1995 and 2012. Their findings
revealed that healthcare is an essential service rather than a luxury and that the prices of
healthcare services of countries depend on the level of the country’s income distribution.
Lower-income level countries tend to have a higher income elasticity of demand for
healthcare services (Baltagi et al., 2017). The cost of healthcare over the years has
increased in the United States and in developing countries alike deterring many people
from accessing healthcare.
During the 67th meeting of the UN General Assembly in New York, all
membercountries passed a resolution in support of universal healthcare systems (Hynes,
2013).

97
The tenets of the resolution emphasized and encouraged member-countries to provide and
deliver affordable and quality-driven healthcare services to all individuals to help to
achieve the UN Committee’s goals (Hynes, 2013). Hynes added that the resolution
directed member-states to roll out health care policies that do not require healthcare
consumers to pay for important medical services because expensive out-of-pocket
payments can deny poor people quality healthcare access. The UN Committee admitted
challenges facing universal healthcare accessibility but stated that universal healthcare is
worth pursuing as it is the foundation of sustainable development and a means for poverty
reduction. About 150 million people each year face difficulties to pay their medical bills
worldwide and many must sell their assets or go into debt to offset their healthcare bills
(Hynes, 2013).
Murtaza (2020) used the Lee’s push/pull model to explain that United States has
been on top in the world for receiving immigrants since 1970. The immigrants are
motivated to migrate to the United States because of availability of healthcare facilities,
services, and economic opportunities (International Organization for Migration, 2020;
Justice for Immigrant, n.d; Murtaza, 2020). Murtaza further explained that Mexico is the
second largest country of origin for immigrants after India. To collaborate Murtaza, the
report of IOM in 2020 stated that 11.8 million Mexicans migrated out of Mexico and 17.5
million Indians left for abroad in 2019. Using Lee’s push and pull theory, Murtaza
demonstrated that people migrated from different places like Africa, South America, and
Asia because of lack healthcare services and facilities to the United States for quality
healthcare services and better life.

98
Healthcare Access in Mexico
Many countries, including Mexico, still face challenges for ensuring universal
health coverage following the UN’s resolution and the Group of Twenty’s (G20)
declaration and commitment to providing universal health coverage (Hone &
GómezDantés, 2019). Mexico has been in the spotlight related to its effort to expand
quality universal healthcare among its citizens. Hone and Gómez-Dantés (2019),
Martinez-
Martinez and Rodriguez-Brito (2020), Rivera-Hernández et al (2019), and Sosa and Sosa-
Rubi (2016) identified these challenges to include difficulty in examining the term
“universal,” providing “quality healthcare” services, not just access, what type of medical
services to provide, lack of political consensus, and lack of resources. According to
Pelcastre-Villauerte et al. (2017), in Mexico, 73% of the population live below poverty
and face challenges to get insured.
According to Hone and Gómez-Dantés (2019), over the years, Mexico has been
advancing healthcare as a social right, expanding healthcare to the uninsured, and has
invested in infrastructure. The provision of healthcare services in Mexico can be acquired
through public or private insurance, but most of the services are provided under Popular
Insurance, known in Spanish as Seguro Popular (S.P.; Hone & Gómez-Dantés, 2019;
Martinez-Martinez & Rodriguez, 2020; Sosa & Sosa-Rubi, 2016). In May 2003, the
government of Mexico established the S.P. to extend quality healthcare insurance to the
poor, underinsured, and uninsured, to address inequities in quality healthcare access. This

99
was done in line with the 1983 Amendment of Article 4 of the Mexican Constitution to
provide universal health care for every citizen (Guerra et al., 2018).
Unfortunately, the program failed, and many people still lack health insurance and
access to quality health care services (Hone & Gómez-Dantés, 2019; Sosa & Sosa-Rubi,
2016). Only 42.2% of the poor that lack permanent jobs are covered by the S.P. health
insurance in Mexico (Martinez-Martinez & Rodriguez, 2020). The Mexican Institute of
Social Security (IMSS), which provides health insurance for only private companies’
employees, covered only 36.4% of eligible enrollees as many eligible enrollees sought to
be covered under S.P., which is relatively cheaper than the IMSS (Guerra et al., 2018;
Martinez-Martinez & Rodriguez-Brito, 2020). However, the S.P. is not resourceful to
insure them.
Although there exists evidence that S.P. has increased health insurance coverage
among the poor, Mexico has one of the highest out-of-pocket healthcare expenses among
the countries belonging to the Organization for Economic Co-operation and
Development (Martinez-Martinez & Rodriguez-Brito, 2020). Despite the improvement in
healthcare insurance, inequities in healthcare provision and utilization still exist because
of lack of resources, corruption, and inefficiency of the government (Hone & Gómez-
Dantés, 2019; Rivera-Hernández et al., 2019; Sosa & Sosa-Rubi, 2016). Lack of
resources, such as inadequate health personnel, finance, and healthcare facilities
especially in the rural areas have affected accessible healthcare in Mexico (Hone &
Gómez-Dantés, 2019; Rivera-Hernández et al., 2019; Sosa & Sosa-Rubi, 2016).

100
Conceptual Framework
Lee’s push and pull theory served as my research lens. Lee (1996) and Liang
(2006) stated that Ravenstein, who has been considered the originator of the theory of
migration and expert in a social movement, defined migration as moving from one
location to another location as a resident for pressing issues. There are two basic types of
migration; inter-migration (between countries) and intra-migration (within one country;
Lee, 1996; Waldinger et al., 2008). Waldinger et al. (2008) emphasized that the theory of
migration is broadly perceived on basis of international migration which is driven by a
country’s economy, healthcare, political, racial, and cultural identities, and tolerance.
Lee on April 23, 1965, at the Annual Meeting of Mississippi Valley Historical
Association, Kansas City, presented an academic paper on migration and why people
immigrate or emigrate (Lee, 1996). Lee explained that social migration is premised on the
push and pull factors with intervening obstacles in the middle. For the push factors, Lee
referred to undesirable conditions such as poor healthcare, poverty, fear of political
persecution, and famine that force people to leave their homes for other places. The pull
factors are conditions such as good health, peace, good jobs, and prosperity that induce,
motivate, and attract people to places (Lee, 1996). While the push factors are associated
with the place of origin, the pull factors are related to the place of the destination. Lee
stated that the decision of a person to migrate is based on four factors: (a) push factors
associated with the area of origin, (b) pull factors associate with the area of destination,
(c) intervening obstacles, and (d) personal reasons (Lee, 1996).

101
Murtaza (2020) investigated causes of international migration and used Lee’s push
and pull theory as a framework. In this work Murtaza mentioned availability of healthcare
services as a pull factor for migration to the United States and lack of quality healthcare
facilities as push factor. Wurie (2012) also used Lee’s push and pull model to demonstrate
reasons Latinos in Cuba, Mexico, and El Salvador came to the United States. Justice for
Immigrants (2017) also used Lee’s push and pull theory to illustrate the difference
between push and pull factors on international immigration. Faridi (2018) explained that
Lee’s theory of push/pull is one of the best models of theories of migration. Faridi added
that the push/pull theory examined causes of migration both at the place of origin and
destination. Faridi further implied that lack of healthcare services may push people out of
their places and available healthcare services attract immigrants as a pull factor. Justice for
Migrants (2017) illustrated how lack of healthcare services and availability of healthcare
services can serve as push and pull factors under Lee’s theory (See Figure 2).
Figure 2
Push/Pull Factors of Immigration
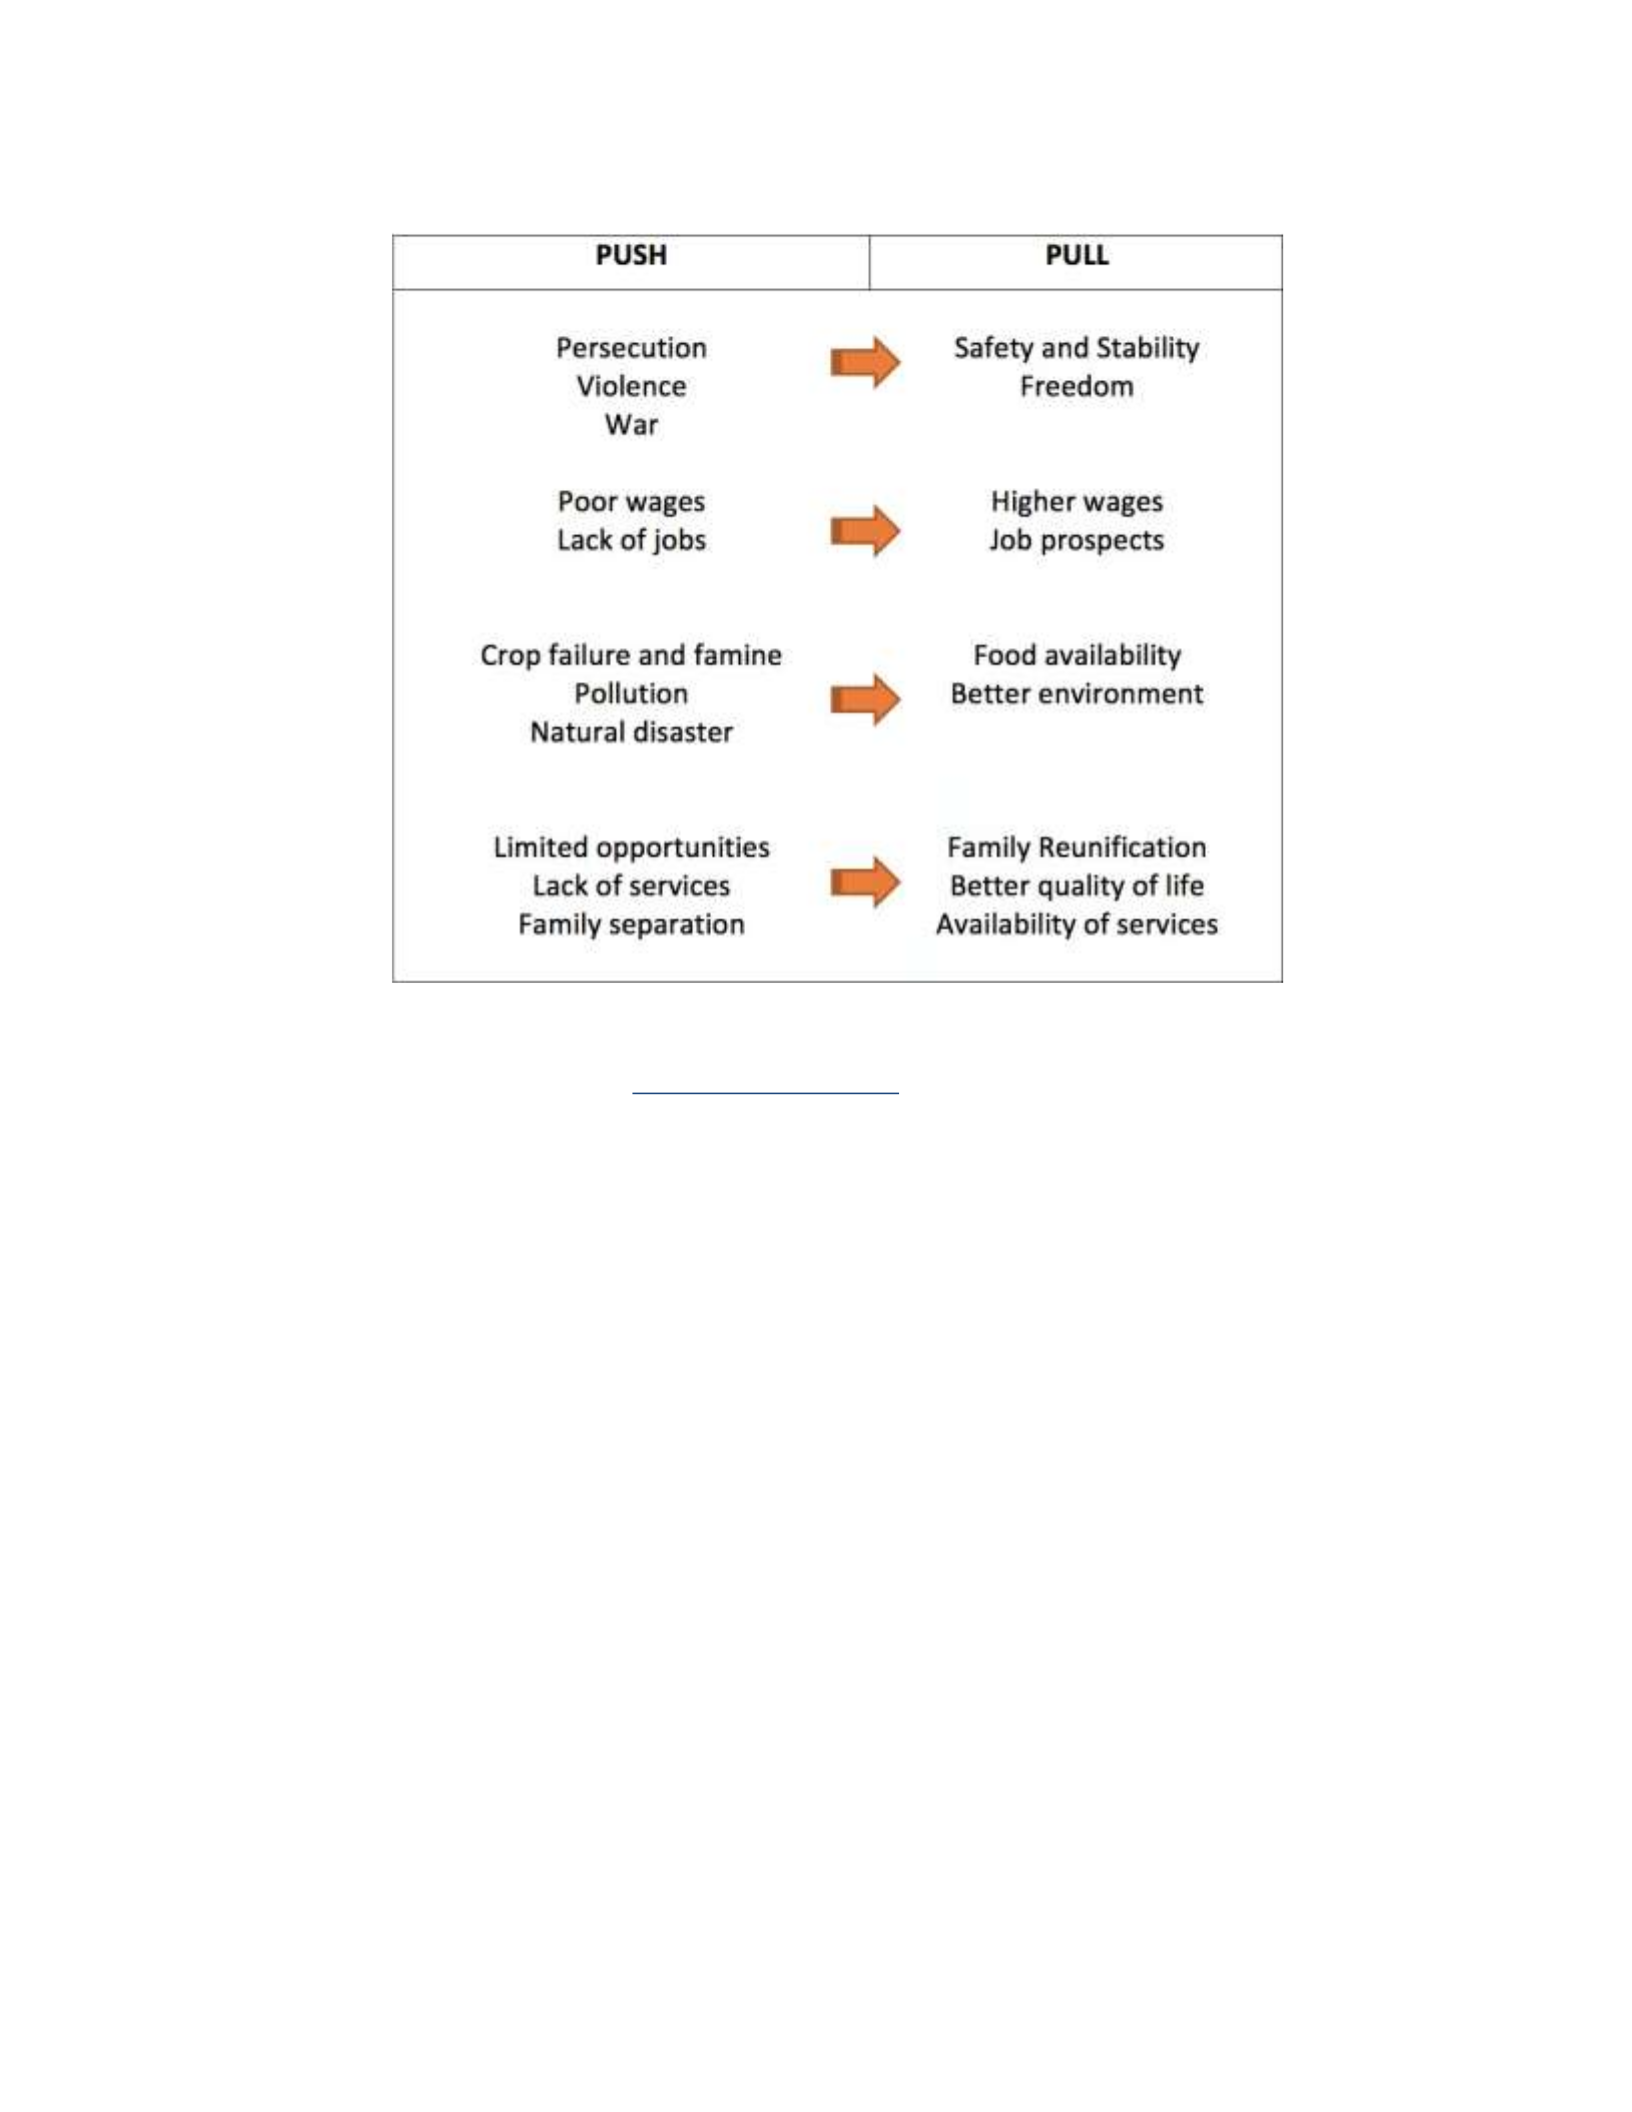
102
Note. Lack of services as push factors refers to lack of quality healthcare services and
facilities in original location. From “Root Causes of Migration” by Justice for
Immigration, 2017, https://justiceforimmigrants.org/what-we-are-
workingon/immigration/root-causes-of-migration/#_edn14. Public Domain.
Problems of accessing healthcare insurance in Mexico may be encouraging people
to enter the United States as undocumented immigrants to have access to free or lowercost
quality healthcare services. The challenges of health insurance in Mexico may be seen as
the push factors and the free and lower cost of healthcare services for undocumented
immigrants in the United States through limited government programs may be seen as the
pull factors as explained in Lee’s theory. The intervening obstacles may refer to border
security, distance, and transportation challenges. The personal factors refer to the
individual perceptions of both the push and pull factors.

103
Methodology and Approach
I employed a phenomenological approach to explore and examine lived experience
of the research participants on the quality of healthcare in Mexico in undocumented
immigration to the United States. According to Denzin and Lincoln (2008), Husserl was
considered the father of phenomenological approach because he used the approach to
conduct many research studies on the behavior and lived experiences of people.
Moustakas (1994) phenomenology research makes it possible for a researcher to actively
engage participants to explore lived experience on concerning social issues. Moustakas
further explained that under phenomenological research, a researcher should focus on
personal observations, participants’ experiences, and emotions to make meanings.
Phenomenological research also focuses on listening, documenting, and interpreting lived
experiences and behaviors in real life (Moustakas, 1994; Patton, 2015; Ravitch & Carl,
2016; Sloan & Bowe, 2014). Moustakas and Ravitch and Carl (2016) summarized
phenomenology characteristics to include: (a) focuses on meanings of lived experiences,
(b) aligns with qualitative research method, (c) does not predict relationships between
variables as in quantitative research, (d) the approach fully engages research participants
attention as they account their experiences, and (e) the approach focuses on meanings and
not how frequently an event occurs or is repeated.
Wurie (2012) conducted a qualitative study and used the phenomenology approach
with 7 participants. The study focused on exploring the lives of Salvadoran families after
the implementation of IIRIRA. This study is similar to my study as both focus on
exploring lived experience of a particular group of people (immigrants) in the United

104
States. While Wurie’s population was the Salvadoran community, mine will target the
Mexican immigrants in the United States. Hall (2010) employed a phenomenology
approach to understanding the challenges of homeless individuals towards
selfindependence. Hall also used this approach to elicit lived experience of homeless
people as I intend to use it to understand lived experience of immigrants on healthcare
insurance challenges in Mexico to undocumented immigration in the United States.
Finally, another important literature review on the approach is the work by Davis and Erez
(1998). These authors used a phenomenology approach to examine the lived experiences
of immigrants towards the multicultural criminal justice system in the United States. I
have the same reason to use the phenomenology approach as the authors, but the
difference is the target population. For these notions, I used a phenomenology approach to
provide in-depth accounts of Mexican immigrants on healthcare insurance challenges in
Mexico to undocumented immigration in the United States.
Summary and Conclusion
As articulated in chapter 2, undocumented immigration has been an issue in the
United States and nearly 11 million undocumented immigrants are living in the United
States making it difficult for the government to track the exact population. The growing
number of undocumented immigrants over the decades has put pressure on social service
and welfare programs and the inflow of narcotic drugs through the southern U.S.Mexican
border. This chapter presented a literature review on focused immigration patterns,
specifically undocumented immigration to the United States, and its effects and efforts
made to prevent or reduce undocumented immigration by the Trump

105
Administration.
This chapter also covered a literature review of healthcare insurance in Mexico
and its challenges. Lee’s push and pull theory served as my conceptual lens. The theory
posits that people begin to move to different places because of push and pull factors. Lee’s
push and pull theory is appropriate and aligns with the purpose of the study. The study
focused on exploring undocumented immigrants’ experience on the role of quality
healthcare in undocumented immigration to the United States. Chapter 3 contains
information describing my methodological approach to explore the lived experience of
undocumented U.S. immigrants. Chapter 3 outlines the research design, sample size,
processes for participant selection, instrumentation, the procedure for data collection,
plan for data analysis, ethical issues, and issues of trustworthiness.
Chapter 3: Research Methodology
Introduction
This study relied on a phenomenological research approach to elicit a detailed
lived experience of Mexican immigrants on problems of health insurance in Mexico as a
driver for undocumented immigration to the United States. I explored the lived
experiences of adults who have immigrated to the United Status in a previous
undocumented status to provide an in-depth look at information regarding healthcare
access as a driver for their immigration journey. This chapter elaborated on the research
questions, interview questions, qualitative methodology, role of the researcher, procedures
of data collection, ethical concerns, phenomenology inquiry, validity, reliability, and
conclusion.

106
Research Design and Rational
Research Question
The main research question was: What are the lived experiences of formerly
undocumented Mexican immigrants living in Hidalgo County, Texas, regarding the role of
healthcare in their decision to migrate to the United States?
Qualitative Method
I relied on a phenomenological design to investigate the lived experience of
Mexican immigrants on the role of health insurance problems in Mexico in relation to its
push factors for undocumented immigration to the United States. Denzin and Lincoln
(2009), O’Sullivan et al (2017), Patton (2015), and Ravitch and Carl (2016) opined that
phenomenological focuses on eliciting and interpreting lived experiences and narrations
while the quantitative method is appropriate for studies that focus on testing hypotheses to
understand causal relationships between variables or phenomena. O’Sullivan et al and
Ravitch and Carl did further explain that the choice of research method is determined by
the nature of the research question. If the research question is exploratory and seeks to
provide in-depth information about a problem, the appropriate research method is
qualitative (Denzin & Lincoln, 2009; O’Sullivan et al., 2017; Ravitch & Carl, 2016).
Based on this and the purpose of my research, the appropriate method I used is the
qualitative method.
Phenomenological Research
Phenomenology is one of the approaches of qualitative research. It focuses on
listening, documenting, and interpreting lived experiences and behaviors in real life

107
(Moustakas, 1994; Patton, 2015; Ravitch & Carl, 2016; Sloan & Bowe, 2014). According
to Denzin and Lincoln (2008), Husserl was considered the brainchild behind the
phenomenology approach as he used the approach to conduct research on the behavior
and experiences of people. Moustakas (1994) explained that under phenomenological
research, a researcher should focus on personal observations, participants’ experiences,
and emotions to make meanings. McNabb (2008) added that phenomenology is utilized in
social research to find social meanings of problems, activities, arts, and work. This has
justified my intention to use the approach to explore lived experiences of Mexican
immigrants on the role of healthcare quality in undocumented immigration to the United
States.
The Role of the Researcher
My interest is to involve communities in identifying social problems related to
healthcare and finding solutions to the problems through empirical inquiry. I used
interviews to elicit lived experiences of the research participants. My role in the process
was to recruit participants, interview them using a semistructured question list, listen and
record findings that conveyed their feelings and lived experiences in relation to the role of
healthcare insurance in Mexico in undocumented immigration to the United States.
Participant Selection
All participants reside in Hidalgo County, Texas, United States, and initial
recruitment was conducted using a social media platform in which I posted my research
interest in English and Spanish on my personal page seeking participants (see Appendix
A). The target population was legal immigrants from Mexico who entered the United

108
States in an undocumented immigrant status. I used a convenient purposive sampling
technique for recruitment. A convenient purposive technique allows the researcher to
select participants who are knowledgeable and have in-depth information about the topic
(Ravitch & Carl, 2016; Rubin & Rubin, 2012; Sharma, 2017). Individuals who responded
to either the English or Spanish social media recruitment posting were contacted using
direct messaging in the social media application and provided further contact details to
review study inclusion criteria and informed consenting procedures. Date and time
stamping were captured and chronologically utilized for participant selection in the event
the interest exceeds required participant threshold. If social media recruitment efforts
failed to achieve seven potential participants, I had planned to use a snowball recruitment
strategy to enlist additional participants by asking my participants who have completed
the study interview to inform other people about the study and provide them my contact
information or direct them to the social media posting for direct messaging. This snowball
recruitment strategy was not needed as I was able to recruit and retain all seven
participants during the initial recruitment process.
I used a sample size of seven participants. The justification for this can be seen in
the research work of Wurie (2012), where he used the same phenomenological research
and a convenient purposive sampling technique of a sample size of seven adults to
investigate the awareness of the implementation of 287(g) among Salvadoran immigrants
to explore the awareness of 287(g) policies among Salvadoran immigrants in the United
States. The similarity between my research and Wurie’s study is that I also used both
qualitative, phenomenological approach, and a convenient sampling strategy with seven

109
participants. Rudestam and Newton (2007) stated that a recommended sample size for
phenomenological research should range between five to 30 participants. According to
Creswell (2007) the recommended sample size for a phenomenological study is between
five to 25, as far as saturation is concerned. Saturation according to Mason (2010) is the
amount of quality information a researcher needs to provide a detailed and clearer picture
about a topic. Morse contends that a minimum of six participants are required for a
proper phenomenological study to be conducted (Mason, 2010). Therefore, my sample
size was seven participants. Another reason is that qualitative study focuses on credible in-
depth information, but not frequencies and generalizations (Mason, 2010; Ravitch &
Carl, 2016).
I understand the vulnerable nature and welfare of the participants. The
immigration legal status of the participants makes them vulnerable and revealing this
confidential information will subject them to possible legal suits, jail time, and
deportation. To protect and keep them safe, I will not reveal any information on their legal
status nor reveal any confidential information that may jeopardize participants’ welfare. I
will assign participant pseudonyms to conceal their identities.
Instrumentation
I used phone interviews to explore my research question. Smart phone and internet
platform interviews were conducted using a qualified Spanish interpreter for participants
wishing to conduct their interviews in Spanish. Using a three-way smartphone calling
feature, I initiated a call first with my Spanish interpreter and then add the participant to
the call. The participant was asked if they wish to conduct the interview in English or

110
Spanish. For those expressing their request to conduct in English, the Spanish interpreter
exited the group call. For those wishing to conduct the interview in Spanish, the interview
proceeded with the Spanish interpreter present. For interviews conducted using an
internet-based connection tool each attendee will be provided a conference access link to
join at the prearranged access time. Interviewing is one of the many ways to collect data
for qualitative studies (Jacob & Furgeson, 2012; Rubin & Rubin, 2012). Interviewing is
the most appropriate tool because my study uses a phenomenology method, which focuses
on exploring in-depth human experience with interest phenomenon (Patton, 2015). The
semistructured interview gives participants enough time and flexibility to expand their
answers and provide detailed information (Rubin & Rubin, 2012). It also allows the
researcher to ask probing or follow-up questions for clarity (Rubin & Rubin, 2012). On
these notions, I used a semistructured interview to explore my participants' lived
experiences and allow them to provide indepth information on the topic. But Ravitch and
Carl (2016) and Rubin and Rubin (2012) cautioned that researchers using semistructured
interviews should remain focused and take control of the process in line with the research
question. According to Jacob and Furgeson (2012), interviewing makes it possible for
participants to share their stories in detail for quality information.
I formulated my interview questions (see Appendix B) to align with my research
question based on the existing interview question from existing scales and studies and the
tips provided by Jacob and Furgeson (2012). I also reframed some focus group interview
questions of Betancourt et al. (2015) for Somali refugees to create the first, second, and
third questions. I also revised interview questions on accessible healthcare in Mexico

111
(Martinez-Martinez and Rodriguez-Brito,2020) to formulate question 2 and 3. I
formulated question 4, 5,6,7, and 8 based on Lee’s push and pull theory, the work of
Murtaza (2020), and Wurie (2012).
The first question of the interview questions intended to gather information about
the background of the respondents. Jacob and Furgeson (2012) explained that the
background questions help the researcher to warm up participants and facilitate the
selection process. The information I obtained help me to determine whether participants
have met selection criteria based on age and birthplace or country of origin. The second
and third questions dealt with accessibility of health insurance in Mexico and its
challenges. Question four covered the benefits of healthcare in the United States and how
they motivate immigrants as pull factors. The fifth question sought information about how
participants came to the United States because of cheaper and accessibility to healthcare.
The final question centered on the differences between health insurance accessibility in
Mexico and health insurance accessibility in the United States.
Interview questions should be open-ended and clear to understand (Ravitch &Carl,
2016; Rubin & Ruin, 2012). The questions should not be leading respondents to specific
responses, nor should clues about possible responses be embedded within them (Rubin &
Rubin, 2012). The construction of the interview questions should not contain words that
may trigger passions, inflate emotions, or disrespect respondents (Rubin & Rubin, 2012).
The other data sources I included are declassified information from the website of U.S.
DHS regarding undocumented immigration on the southern border. This created an

112
opportunity for triangulation of all the sources of data for valid and credible data
(Shenton, 2004).
Procedures for Data Collection
Following the recruitment process above, I emailed an informed consent in both
English and Spanish wherein the purpose of the research is explained in more detail to
include participants’ rights and the voluntary nature of their participation to include the
right to withdraw from the interviews at any time and the right to skip any question they
feel uncomfortable answering. Participants could schedule the interview for their
convenience after they agree to participate.
According to Rubin and Rubin (2012), recording and transcribing or taking notes
of interviews help the researcher minimizes biases and produces credible findings. I
sought permission to audio record and transcribe the interviews for credible data. I used
the Call Recorder smartphone application to digitally capture telephone interviews for
transcription. For interviews being conducted using internet connectivity tools, I used the
embedded recording features in the digital product to produce data transcripts. For
confidentiality purposes when using an internet-based connecting tool, participants were
advised that they may keep their video cameras off. For those participants who decline to
be audio recorded either during smartphone or interview-based connections, I took
detailed notes throughout the interview process. Participant pseudonyms are used for
confidentiality purpose.

113
Data Analysis Plan
I used the Call Recorder application to record and transcribe phone interviews and
I used embedded voice recording features of internet-based connection tools for
interviews conducted using these interfaces. I took interview notes for those sessions in
which audio recording was declined. Transcription of interviews helps the researcher to
have a vivid understanding of what transpired during interviews and captures exactly what
each participant says (Rubin & Rubin, 2012). Following transcription construction,
I used ATLAS.ti software for coding and data analyses. According to Rubin and Rubin
(2012), coding is one of the first key elements of qualitative data analysis and
interpretation. The ATLAS.ti software is one of the leading software qualitative data
analyses (QDA) tools and it provides researchers with a broad scope of informative
details related to their phenomenon of interest (Boston University, n.d; Predictive
Analysis Today, 2016a). ATLAS.ti also allows researchers to gain in depth information
and to see content patterns bringing meaning to information (Boston University, n.d;
Predictive Analysis Today, 2016a).
Ethical Consideration
My participants are considered vulnerable immigrants and, as such, issues of
privacy and confidentiality are very important. All participants are anticipated to be in a
legal U.S. resident status at the time of interviews. Participants may choose to discuss or
describe their immigration journey; however, I had not explored specific information
regarding immigration status in my interview questions. Informed consent was used to
describe participant rights. Creswell (2007) stated that a researcher should explain the

114
purpose of a study to participants to gain their trust. Participants were assigned
pseudonyms for confidentiality. To achieve this, I allowed participants to choose unique
alphabets other than their real names to conceal their identities. If the selected alphabet
has already been adopted by another participant in a concluded interview, I ask the present
interview participant to select another alphabet. Creswell added that the true names of
participants should not be used to enhance their privacy and confidentiality. I explained to
each participant my study’s purpose and remind them that participation is voluntary, and
any participant is free to quit at any stage of the investigation. According to Ravitch and
Carl (2016) and Rubin and Rubin (2012), it is unethical to lie to participants about a
study’s purpose or force any person to participate in research. My interview questions
were constructed as open-ended questions and were not expected to demean or trigger
respondent emotions. Data protection is the process of ensuring the security of
information obtained from participants to guarantee their safety (Rubin & Rubin, 2012) To
ensure data protection, I removed all information or cues on interview transcript that
might reveal participants’ identity. I only shared the redacted findings and analysis with
the Walden University’s faculty members. I securely stored the contact information of
participants, data, and study analyses on electronic files in Dropbox with a backup file
stored on an encrypted flash drive. I secured the flash drive in my locker I will keep and
protect the data for at least 5 years as required by Walden University. At the conclusion of
the required 5-year storage period, I will destroy electronic data using a disc wipe
software and all information contained on paper will be shredded.

115
Member Checking
I provided each participant an opportunity to member-check their transcriptions to
ensure information has been clearly captured and to validate that confidentially has been
maintained. According to Guba and Lincoln (1985), the member checking technique
allows research participants to check and confirm their answers for credibility and true
representation. After each interview, I gave 30 minutes to each participant to check all
their answers to make sure it is what they want to say. For participants who do not wish to
participate in member checking their transcripts will be accepted as final and used for
analyses. Wurie (2012) used member checking technique to enhance and strengthen data
credibility.
Issues of Trustworthiness
The credibility of qualitative data is equally important as it is in a quantitative
study (Shenton, 2004). For the data of qualitative research to be trustworthy, the
information obtained in the field should be credible, transferable, dependable, and
confirmable (Shenton, 2004). Credibility is the process of revealing what exactly
happened in the field (Shenton, 2004). To obtain credible data, a researcher should use the
triangulation strategy, member checking, peer debriefing, and observation (Shenton,
2004). Lincoln and Guba (1985) and Shenton (2004) explained triangulation as using
many sources of data collection to check inconsistencies. Apart from the interviews, I will
access data from the websites of U.S. DHS, Mexico Health Department, and U.S. BPC to
check insistencies for credible data. I used a colleague student at Walden who is interested
in the topic for peer debriefing. I posted the announcement on Walden students’

116
dissertation groups on Facebook for interested person. The person sent me a private
message on Facebook messenger accepting to debrief my findings. We are not acquainted.
The person signed a confidentiality agreement and focused mainly on checking my
personal biases and perceptions. The debriefing process started soon after interviews were
conducted and ended after data analysis. I emailed the interview notes or transcripts to the
person. I used the member checking technique and according to Shenton, member
checking allows participants to make corrections to reflect what they wanted to say to
make sure the information provided is true.
To achieve transferability which refers to where the findings of one study can be
used in different settings (Lincoln & Guba, 1985; Shenton, 2004), the researcher should
allow participants to provide detailed information about the topic to generalize findings
(Lincoln & Guba, 1985; Shenton, 2004). This is in line with my selected
phenomenological approach. To achieve dependability, which refers to findings being
consistent and can be replicated (Lincoln & Guba, 1985; Shenton, 2004) semistructured
interviews were used to allow participants provide detailed information about the topic.
Finally, the last requirement to ensure data trustworthiness according to Shenton (2004) is
confirmability. This is where the researcher should be neutral to prevent biases and
provide an audit trail of all for the research (Lincoln & Guba, 1985; Shenton, 2004). The
triangulation method also enhances the confirmability of a study (Lincoln & Guba, 1985;
Shenton, 2004) which I employed.

117
Summary
Chapter 3 presented information on the design of the research, role of the
researcher, selection of research participants, and instrumentation. The study’s design is
phenomenology. Convenient sampling is used to select research participants. Recruitment
of participants was done on social media. Interviews were conducted using phone and
other internet-based electronic tools. ATLAS.ti software is used for data coding and
analyses. This chapter additionally described my study’s ethical procedures and issues of
trustworthiness for recruitment, interviewing, coding, and analyses.
The Chapter 4 presents findings of my in-depth interviews, data analyses, and
evidence of trustworthiness of the data collected. The chapter also presents characteristics
and information about the research participants. In this chapter, the responses provided by
the research participants are categorized into themes for easy analysis and understanding.
Chapter 4: Research Findings
Introduction
The study’s purpose was to understand the role of healthcare quality in Mexico in
undocumented immigration to the United States. A phenomenological research approach
was used to explore lived experiences of the research participants. This chapter presents
information about the research participants, their experience with undocumented
immigration to the United States, and healthcare in both Mexico and United States. The
chapter also presents research findings and data analysis.

118
Setting
All the interviews were conducted via phone. In total, seven participants were
interviewed; five participants agreed to speak to me in English while two participants
opted to do the interview in Spanish through the interpreter. Each interview lasted about
45 minutes and additional 30 minutes for member checking was needed once individual
transcripts were transcribed, cleaned, and formatted for sharing with the interviewed
participant.
After I received IRB approval (0986362; 05-26-22), I recruited all the seven
participants using a social media platform. I posted my recruitment announcement
(Appendix A) on my personal page wall. The people who had interest to participate
responded to the posting through direct messaging to my user account name. I then
provided them criteria for recruitment and the informed consent. Each of the seven
recruited participants completed the research interview in its entirety. I made no changes
to the informed consent after IRB approval as I did not change participants’ recruitment
process, data collection methods, analysis, and data storage.
Demographics
All seven study participants lived in the Hidalgo County, Texas, United States.
All the participants are adults who experienced healthcare both in Mexico and United
States. All participants speak English and Spanish and used to have jobs in Mexico. Out
of seven participants only two people did their interview in Spanish. To ensure
confidentiality, I used pseudonyms for all participants interviewed.
John
At his interview time, John was living in Hidalgo County, Texas. He is in his mid

119
40s and currently a truck driver in the United States. He came to the United States from
Mexico. He was truck driver too in Mexico. He had health insurance in Mexico and
currently has health insurance in the United States. John sent me a message to take part in
the study after reading the recruitment posting I posted on my social media page
(Appendix A). During the interview phone call, he declined the interview be
audiorecorded and agreed the interview to be conducted in English. John was polite and
clear during the entire process.
Juan
At his interview time, Juan was living at Hidalgo County, Texas and working as
car mechanic. He is in his early 40s. He immigrated to United States from Mexico in his
early 30s at Tamaulipas closer to the southern border. Juan was a car mechanic in Mexico.
He was fully insured at the time of this study. Juan sent me message after he read my
recruitment posting I posted on my social media page. He turned down my request to
audio-record his interview. He requested the interview to be conducted in Spanish through
the interpreter. His interview was done in Spanish. Juan was nervous when he answered
the interview phone call, but he became calm and relaxed when I started building rapport
and asking questions about his favorite food and car for the first 5 minutes. He was
comfortable, articulate, and audible in Spanish language. His interview lasted about 45
minutes.
Maria
At her interview time, Maria was residing at Hidalgo County, Texas and working
as a nurse. Maria is in her late 40s. In Mexico she was living at Reynosa a city closer to
the Mexican-U.S. border. She came to the United States in her early 30s. She was a nurse

120
in Mexico. Maria who saw my recruitment post in Spanish on my social media page and
sent me a message expressing interest to participate. Before her phone interview started,
Maria explicitly stated he wants the interview to be conducted in Spanish and should not
be recorded. Maria was happy throughout the interview process and was straight forward
in her responses. She was clear. Her interview lasted about 50 minutes.
Rosa
At her interview time, Rosa was residing at the Hidalgo County, Texas. Rosa was a
teacher in Mexico before coming to the United States and she had health insurance. She is
in her early 40s and teaches in middle school in the United States. She immigrated from
Palau Coahuila. Rosa replied to my recruitment post on my social media page and sent me
message expressing her interest in the study. During the phone interview call, she agreed
that the interview should be conducted in English but should not be recorded. She was
clear and detailed in her responses to the interview questions and answer all the questions.
Her interview lasted for about 30 minutes.
Perez
He is in his mid 70s. At his interview time, Perez was living in Hidalgo County,
Texas. He was born in Mexico, but he immigrated to the United States in his early 40s.
He was a welder in Mexico for more than 40 years. He had health insurance in Mexico.
Perez was working as a welder when he arrived in the United States, but now he is retired.
Perez sent me a message after he read my recruitment post on my social media page.
Before the interview started during the interview phone call, Perez opted for English
interview, but turned down my request to record the call. He was so emotional and

121
provided examples for probing questions. He remained calm throughout the interview and
provided concise and clear responses. His interview lasted for about 50 minutes.
Kiara
She is in her late 50s. At her interview time, Kiara was living at Hidalgo County,
Texas and working as nurse. She moved to the United States from Mexico when her
husband had work related accident in Mexico. In Mexico, Kiara used to work in one
factory called Maquiladoras. She had health insurance in Mexico because of her job.
Kiara read my recruitment post (Appendix A) on Facebook and sent a direct message to
me on Facebook. When I called her for the interview, she indicated she wants the
interview to be conducted in English, but she declined the request to record the call. Kiara
was open, detailed, and audible in her responses. The interview with her lasted for about
30 minutes.
Juliana
She is in her mid 40s and at her interview time lives in Hidalgo County, Texas.
Juliana immigrated to the United States from Mexico when she was battling with a
chronic hepatitis B and had medical issues with her liver. Juliana was a working in a
restaurant as waitress. She had healthcare insurance in Mexico. In the United States,
Juliana is working as parole officer. She read my recruitment post on my social media
page and sent me a message to show interest as participant. During the phone interview,
she agreed to speak English and turned down my request to record the call. Throughout
the interview she was calm, happy, and clear. The interview call with Julian lasted for
about 45 minutes.

122
Data Collection
I collected data from seven research participants using the semistructured
interview protocol (see Appendix B) to explore lived experience of the participants. All
the interviews were conducted via phone. Each interview lasted between 30 to 60 minutes.
I scheduled each interview at the convenience and request of each participant. I used 2
weeks to complete the interviews and member checking. Two of the interviews were
conducted in Spanish with professional interpreter and five interviews were conducted in
English. The settings for this were inside my room in Fort Worth, Texas and Hidalgo
County, Texas, for each respondent. All the interview calls initiated well and ended
successfully without any network interference or physical interruptions.
I asked each participant all questions on the interview document (see Appendix B)
and sometimes asked follow-up questions to clarify information or for in-depth
information during interviewing. All the participants separately turned down my request to
audio record the interview calls for privacy reasons. I spent about 40 minutes asking
interview questions and taking interview notes on each call. After the interview, I read the
responses provided to each respondent to confirm or modify their answers to reflect what
they really wanted to say. This member checking process was completed within 30
minutes for each participant. All the participants did the member checking for credible and
accurate data. I also used peer debriefing technique to check my own bias in data coding
and analysis. I converted the interview notes into a MS Word document for each
participant. I stored the data on electronic files in Dropbox (cloud) with backup on an
encrypted flash drive, which I stored in a locked cabinet. Some information about the

123
causes of undocumented immigration from Mexico to the United States was obtained
from the website of DHS. However, I could not assess or obtain information on the
challenges of healthcare accessibility in Mexico on the website of Mexico Health
Department. This was the only variation in the data collection plan outlined in Chapter 3.
Data Analysis
I used ATLAS.ti software to code and analyze the data. After I completed
interviews and member checking to confirm participants’ responses and make corrections,
I converted the interview notes of each participant into MS Word document. I applied the
iterative process (Pietkiewicz & Smith, 2014), which required that I and thoroughly and
closely read and reread the transcript, highlighting experiences of the participants on
challenges of healthcare in Mexico to influence to immigrate to the United States for
healthcare access. As I listened to participants and asked follow-up questions during the
interviews in addition to reading the interview notes I found some statements and words
that helped me to understand the experiences of the participants about the role of
healthcare in Mexico in undocumented immigration to the United States.
Using the ATLAS.ti software, I uploaded each participant’s responses and the DHS
website’s article on undocumented immigration in a form of word document and assigned
codes to the statements related to the research question. For the first cycle coding, I used
descriptive coding method. Here I described each participant’s response with simply
words and statements. For the second cycle coding, I used concept coding where I
assigned concepts to the descriptive statements in the first cycle coding. Finally, I looked
for patterns and similar concepts in participants responses I and grouped those patterns
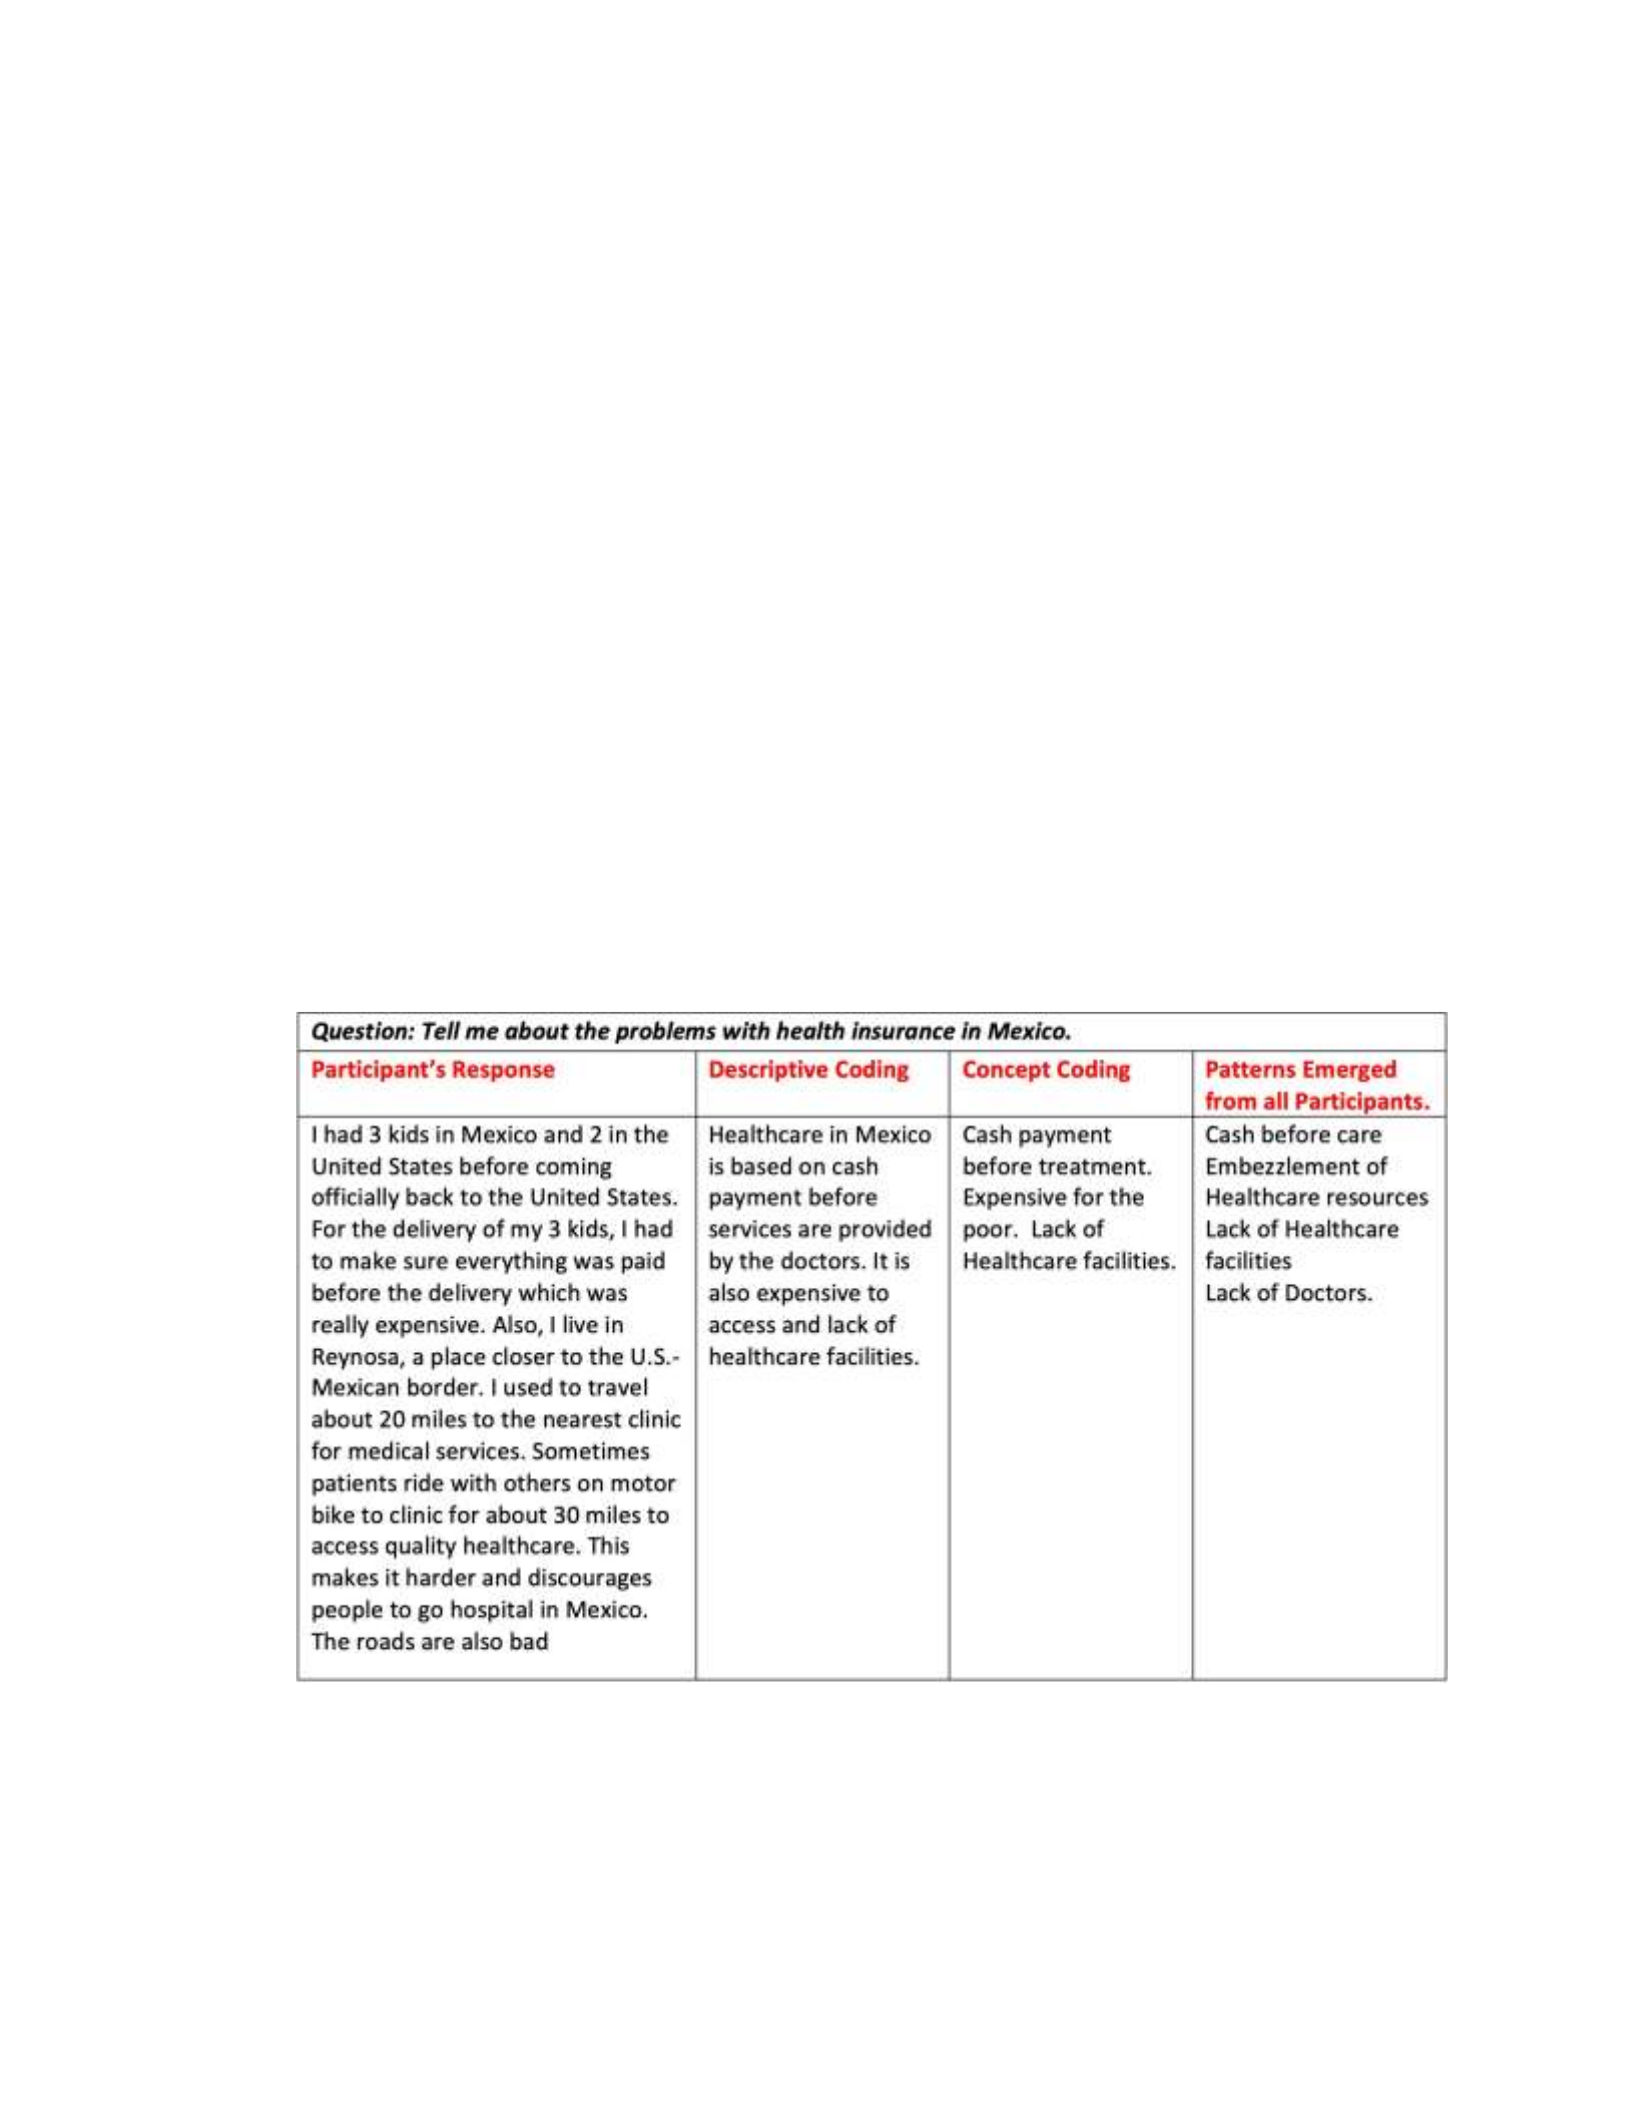
124
into themes. The Figure 3 below illustrated and summarized the coding process I used.
Some of the themes I generated relating to challenges of healthcare in Mexico (push
factors) included: (a) paying cash before receiving medical services, (b) corruption, (c)
lack of hospitals or clinics at the rural areas, and (d) lack of personnel or doctors.
Themes I generated on the pull factors of health insurance in the United States included:
(a) cheaper price, (b) perception of free medical services in emergencies, and (c) quality
healthcare services.
Figure 3
Coding Process
Note. The figure is an output of ATLAS.ti used in the coding. It illustrates the processes
followed. This process was repeated for each participant’s responses to generate the
themes.

125
I noted discrepant views or cases in the data coding and analysis. Patton (2015)
explained that data discrepancy strengthens and shows the in-depth nature of data
patterns. I used the discrepant data to understand and validate different reasons people
have to immigrate to the United States. I compared the discrepant data to the main data
and realized that the discrepant data described availability of jobs as the primary driver of
immigration to the United States. This reason opens the gate for more research to
appreciate and understand the overall picture of immigration.
Evidence of Trustworthiness
To achieve data credibility, I followed the plan I outlined in Chapter 3. To ensure
the data represent the actual view of the research participants, I used a member checking
technique to make sure I read each participant’s answers to them. This process provided
an opportunity for me to make corrections for the data to be credible and reflect what the
participants really wanted to say. I also used triangulation method by comparing data from
the interviews to information obtained from the website of DHS about reasons Mexicans
immigrate to the United States. I also thoroughly compared data of each participant to
ensure consistency and accuracy.
To achieve data transferability, I employed phenomenological research approach
and semistructured interviews. This method allowed the participants to provide in-depth
information and thick descriptions of their experience about the role of health care in
Mexico in undocumented immigration to the United States. According to Shenton (2004)
and Patton (2015) phenomenological study and semistructured interviews allow the
researcher to obtain detailed information to achieve data replicability and generalizability.

126
I also used a convenient purposive sampling strategy to select participants who have more
information about the topic. This helped me to achieve data transferability and
applicability of the findings.
I followed the plan explained in Chapter 3 to ensure data dependability. To ensure
consistency and reliability of my research findings I consulted my committee chair and
committee member when developing the interview questions to make sure all the
questions are realistic, aligned with the research question, and consistent with each other
(see Appendix B). Finally, because I used semistructured interviews, I was able to ask the
participants follow up questions for clarity and more information to make sure my
findings are dependable and consistent.
To achieve data confirmability, I used peer debriefing technique. As I explained in
Chapter 3, I posted the announcement on Walden students’ dissertation groups on
Facebook for interested person. The person sent me a private message on Facebook
messenger accepting to debrief my findings. The process started when I completed
interviews and ended when I finished data analysis. The peer reviewer double checked
interview notes, codes, and interpretations to make sure they are free from my personal
bias. Moon et al. (2016) explained that for data to be considered reliable, the researcher
must provide a detailed description of the methods, procedures, and processes used in
drawing conclusions for potential replication by others. All these procedures are explained
in Chapter 3. I also used member checking technique and research reflexibility on my
personal beliefs and perception to be neutral and transparent in data collection and
analysis to maximize confirmability.

127
Results
My research question was: What are the lived experiences of formerly
undocumented Mexican immigrants living in Hidalgo County, Texas, regarding the role of
healthcare in their decision to migrate to the United States? I used semistructured
interviews to explore lived experiences of the research participants. The data were
organized in MS Word document. I used ATLAS.ti software, descriptive and concept
coding strategy to code the research data. The themes that merged relevant to the push
factors included: (a) paying cash before receiving medical services, (b) corruption, (c)
lack of healthcare facilities at the rural areas, and (d) lack of doctors. These problems as
push factors, forced some participants to leave Mexico. The other themes that were
generated relating to the pull factors of healthcare insurance in the United States are: (a)
cheaper health insurance for healthcare, (b) perceived free medical services in
emergencies, and (c) quality healthcare services. The pull factor themes motivated and
encouraged some of the participants to migrate to the United States to access quality
healthcare. The study’s push/pull factor themes and discrepant data are discussed in this
section.
Theme 1: Pay Cash before Receiving Medical Services
The study’s findings revealed that the role of healthcare in Mexico in
undocumented immigration to the United States is, that people in Mexico more at times
are required to pay upfront for medical services even though they are insured. Based on
the comments by the respondents to pay cash before seen by a physician limited access to
quality healthcare especially the poor. Five of the seven respondents shared their views.

128
For instance, Juan noted “in order to have health insurance in Mexico you need a job.
Health insurance in Mexico is all about money and no doctor will you see you without
money even when you have insurance.” He added, that in Mexico to have any medical
procedure done you need to have the money right there and then. You cannot have any
medical procedure done without the money.
Maria stated “I had 3 kids in Mexico and 2 in the United States before coming to
the United States. For the delivery of my 3 kids, I had to make sure everything was paid
before the delivery which was really expensive.” According to Perez, it is hard to obtain
health insurance in Mexico, even if you have insurance everything is expensive. Rosa
summarized her experience in Mexico about paying cash before a doctor attend to you.
She stated “sometimes my doctor would ask me to buy injections from pharmacy and
bring them to the hospital for injection or treatment. It was appalling and disgraceful.”
Finally, commenting on the challenges of health insurance in Mexico, Kiara explained that
“in Mexico my insurance really didn’t cover anything, I had to pay everything upfront
even for the deliveries of my babies. I was always scared of needing emergency insurance
due to the money.” She expressed her view that physicians or nurses in Mexico have
prioritized money over human life and welfare.
Theme 2: Corruption and Embezzlement of Public Funds or Resources
All the 7 participants described how corruption and embezzlement of public
resources made it difficult for healthcare access in Mexico. John felt that many people in
Mexico have no access to healthcare because some politicians and public administrators
used public funds meant for expanding healthcare access for personal gains. He stated

129
“politicians and administrators in Mexico are corrupt to the core. The empty public coffers
for personal gains to the detriment of the poor to access quality healthcare.” Juan asserted
that corruption is the root cause of ineffective health insurance system. He narrated “my
friend used to tell me how some administrators in the Health Ministry in Mexico always
channel public funds meant to help the vulnerable to access healthcare for personal
benefits.” He described the situation as a “curse.” Maria who shared similar view with
Juan on corruption further explained that “everything is already planned out about making
it difficult for the poor to always suffer and the rich corrupt politicians continue to be
rich.” She felt the situation is unfair and disgusting.
Perez was emotional in describing the impact of corruption on healthcare access.
He stated “in Mexico corruption is bad, I don’t like talking about it; it’s politics. I try to
not get involved in them.” Even though he was not interested in talking about corruption,
he described it as a “sin” against the public and vulnerable as it denied them basic right to
have access to quality health care. Expressing her experience Rosa explained that
corruption is the main challenge for the people to access health insurance as corruption
leads to inadequate funds to expand access to healthcare. Kiara noted “public
administrators in charge of managing public funds for public good are rather using the
funds to buy nice houses and luxury cars draining the coffers meant to help expand health
care to the people at the rural areas and pay physicians.” Juliana had a moment to reflect
on her experience on corruption as a problem of health insurance in Mexico. She said her
father one narrated to her how politicians in Mexico have been using state resources for
personal gains. She lamented “One of the biggest problems of insurance in Mexico is

130
corruption.” She defined corruption as a situation where a public official uses public
resources such a money to satisfy his/her parochial interest while the vulnerable continue
to suffer.
Theme 3: Lack of Healthcare Facilities at Rural Areas
Four out of seven participants mentioned lack of healthcare facilities in rural areas
as one of the challenges of healthcare access in Mexico. Maria stated “I live in Reynosa, a
place closer to the U.S.-Mexican border. I used to travel about 20 miles to the nearest
clinic for medical services. Sometimes patients ride with others on motor bike to clinic for
about 30 miles to access quality healthcare. This makes it harder and discourages people
to go hospital in Mexico.” She added that some roads to certain clinics are nonmotorable.
According to Perez, inadequate number of health facilities leads traveling long
distances to access healthcare discourages some people to go to hospitals to seek
treatment. He stated, “healthcare facilities are congested in urban areas or cities, but many
rural areas lack clinics and hospitals and even roads leading to the few healthcare facilities
in the rural areas are deplorable.” He explained further that nurses and physicians do not
want to station at rural areas to provide quality healthcare to people who need as every
nurse and physician want to work in cities. These challenges increase waiting time to see a
nurse or doctor. Perez narrated that 50 years ago he visited a clinic in and waited a long 3
hours in a line to see a nurse. Finally, he and other 3 patients had to go back home without
seeing any nurse or attended to.
At Tamaulipas, closer to the Mexican-U.S. border, Juan explained that
unavailability of healthcare facilities such as clinics and hospitals denied some people to

131
access healthcare. He said he used to traveled long distance for about 3 hours on motor
bike to the nearest hospital to seek treatment. Juan posed an important question in
explaining his answer. He stated, “imagine what happens to patients who lived in my area
but who do not have motor bikes or cars to travel to the nearest hospital?”. Finally, in
addressing the question concerning challenges of healthcare access in Mexico, Juliana
explained that she used to travel about 6 miles on foot to the nearest hospital to access
healthcare. She stated “I went through hell” because of inadequate number of hospitals
and clinics in Mexico and lack of means or transportation to go to the clinic or hospitals.
Theme 4: Lack of Doctors
In explaining challenges of healthcare access, three out of seven participants
narrated their experience about lack or shortage of healthcare personnel affected their
access to healthcare in Mexico. In accounting her experience, Kiara stated “not having
enough doctors and nurses at hospitals and clinics is another problem making it harder on
people to access healthcare in Mexico. This results in long hours to see physicians and
nurses when you visit a facility. I remember on about three instances I had to wait in line
for more than 2 hours to see a doctor. It was terrible.”
Juliana explained that healthcare access is essential but lack of nurses and
physicians in Mexico has denied many people to access quality healthcare. She stated that
during the time she was diagnosed with hepatitis B she would go to a public hospital for
checkup and the doctor would not show up or she could wait for about 3 hours, because
the doctor had private hospital to attend to patients in that hospital. According to Juliana it

132
is because of lack of doctors in public healthcare facilities that made her experienced what
she explained, and it is a challenge for accessing quality healthcare in Mexico.
Finally, Rosa also shared her experience about lack of doctors in public hospitals
as a problem of healthcare access in Mexico. She narrated “before I immigrated to the
United States, there was doctor in my community’s government hospital in Mexico. The
hospital only had nurses who are not trained to do surgeries and other complicated
medical conditions.” She explained further that lack of specialists in hospitals discourages
people to visit hospitals when they are sick and that complicates medical conditions
needing more attention and money for treatment.
The themes that were generated as pull factors of immigration to the United States
from Mexico for healthcare access are discussed below: it was a probing question put
before all participants.
Theme 1: Perceived Free Access to Healthcare in Emergencies
During the interviewing four out of seven participants explained their experience
as undocumented immigrants about free access to healthcare in emergencies is a pull
factor for immigration to the United States from Mexico. Kiara accounted that: I knew
as an undocumented I could go by the hospital anytime and I would be given healthcare
access without insurance if my medical condition is critical. And
I would not pay anything to see a doctor in emergency which is not possible in
Mexico.
She added “If I’m honest I feel safer in the United States than Mexico.” She also added:
My husband had a lot of health problems and while living in Mexico we couldn’t

133
afford anything. We decided to move to the United States because of him, he had
more access to healthcare here through the help of some organizations. He passed
away about 3 years ago due to a work accident, he wasn’t denied healthcare access
due to no insurance. He was even transported via a helicopter to another city end
up to this date we have not been charged a single dime for it.
Maria also said
When I came to the United States before I become legal permanent resident, I had
2 surgeries as emergency and did not pay nothing. I also had my two daughters
here; I wasn’t expected to pay anything for them as well. On the contrary I was
given health insurance and for my baby while I was pregnant. Both of my kids had
access to free Health insurance which was a great benefit. In the United States the
healthcare services are more quality than services in Mexico. They have better
medicines and doctors and equipment.
Rosa also explained that when she arrived in the United States from Mexico:
I was able to see that in the United States health insurance access was way easier. I
did not have health insurance here yet due to being illegal, but I went the hospital
anytime and I would be given healthcare access without insurance in life
threatening situations. And I would not pay anything to see a doctor under
emergency which is not possible in Mexico.
Finally, during the interview process Juan also shared “I moved to the USA because of job
and healthcare access. Health insurance in the United States is more accessible. If I need
to go to the hospital, I don’t have to worry about having to pay before being seeing a

134
doctor. I was admitted to emergency room when I had car accident. I did not pay any
money before I was attended to. There is quality healthcare.”
Theme 2: Cheaper Health Insurance for Healthcare
Three of the participants explained that undocumented immigrants in the United
States buy health insurance at cheaper rates compared to documented immigrants and
citizens. According to Maria, it is not expensive for undocumented to buy health insurance
as some non-profit organizations help undocumented to acquire insurance. She noted
“many healthcare centers here funded by the federal government offered health insurance
at cheaper rates to the poor including the undocumented immigrants. After my surgeries as
an undocumented I bought health insurance at rate of $40 a month at Hidalgo Health
Center which is more expensive for documented immigrants and citizens who work.”
Juan narrated that accessing healthcare is cheaper for undocumented immigrants in
the United. She stated “there are independent charity organizations like Kaiser
Permanente Bridge Program which made me to apply for low-cost medical services. You
don’t need a social security number to apply. I applied and was approved. I paid $35 a
month just for primary healthcare services”. The enrollment helped me a lot to access
healthcare at lower prices when I was undocumented.
Finally, in the interview Rosa shared her experience that as an undocumented,
accessing health care insurance is cheaper and easier for her. She explained that some
health facilities and hospitals receiving some federal funding provide health insurance at
cheaper rate to poor person including undocumented immigrants who cannot afford to pay
for higher rates. She continued “for instance when I arrived in the country as

135
undocumented the Catholic Church, I attend, provided me the necessary financial help to
acquire health insurance and later I bought insurance at cheaper rate of $40 a month until I
become documented.” Healthcare services were also provided by newly trained doctors at
San Antonino hospital at lower cost or free to poor people and undocumented immigrants
according to Rosa.
Theme 3: Quality Healthcare Services
All seven participants agreed and stated that there are better quality healthcare
services in the United States than in Mexico. However, four out of seven participants
admitted that the availability of the quality healthcare services in the United States
influenced their decisions to relocate to the United States. Maria is noted to have explain
that there are better doctors, machines and medicines in the United States compared to
Mexico and everyone is interested in accessing what is better. She added that she had two
surgeries as an undocumented immigrant in the United States and had seen better
equipment, doctors, and medicines in the whole process. According to her Mexican
hospitals and healthcare facilities lack some of these equipment, specialized doctors, and
medicines.
Kiara also indicated that quality of healthcare services is better in the United
Sates than Mexico because of the technology gap between Mexico and United States.
Rosa also mentioned that she migrated to the United States because she believed there are
better doctors and medicines in the United States and that is proven when she visited
hospital for the first time as undocumented immigrant. She said, “the doctors were nice
and kind to me and would speak soft words to me and give me hope all the time but in

136
Mexico sometimes doctors would be treating me like trash and don’t care about I feel”.
Finally, Juan also mentioned that she moved to the United States because of healthcare
access. She explained that United States has more sophisticated and modern medical
machines and tools and more specialized doctors than Mexico. She narrated “I feel safer
and confident in the quality of healthcare I received in the U.S. than in Mexico even
though sometimes it is more costly than Mexico. However, in all U.S. is better than
Mexico in terms of quality of healthcare access. Figure 4 below summarized themes of
the research findings by illustrating reasons some of the participants migrated from
Mexico to the United States.
Figure 4
Push/Pull Factors of Migration
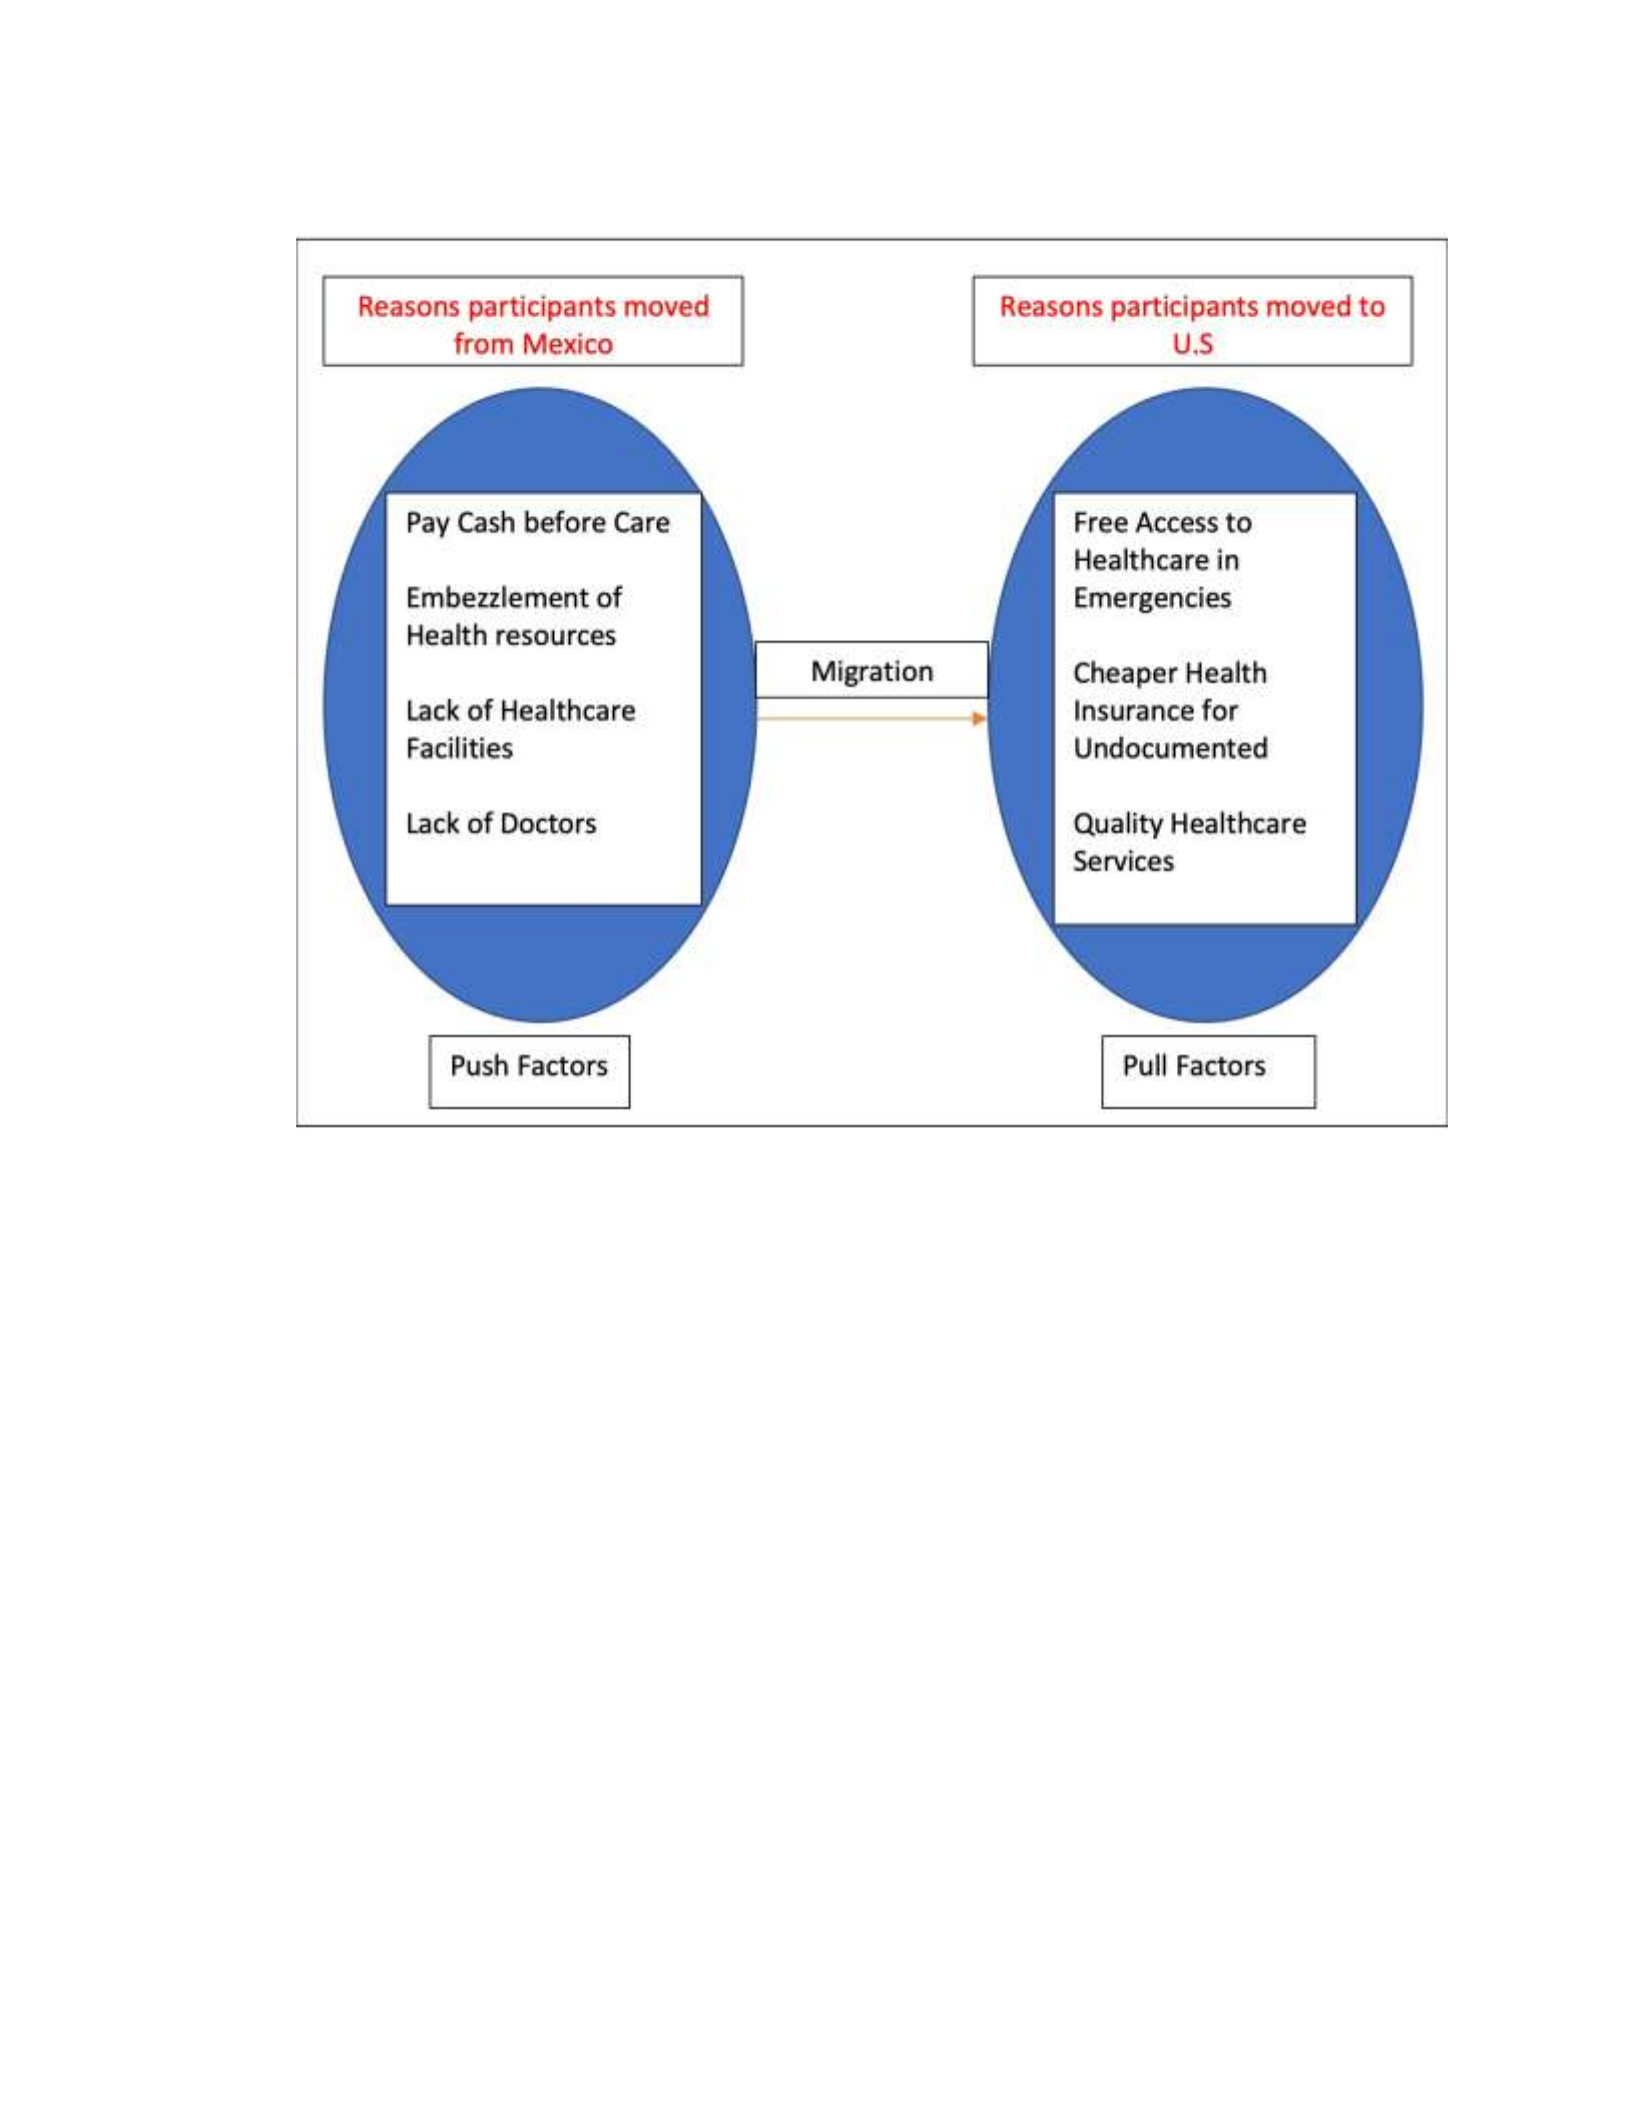
137
Note. The figure illustrates reasons some of the participants migrated from Mexico (push
factors) and reasons they migrated to the United States (pull factors) for healthcare access.
Discrepant Data
Discrepant data is normal in research studies and proves quality of data (Miles et
al. (2014). During the interviews, three out of seven participants explained that they
moved to the United States because of jobs opportunities and reuniting with families, but
not because of healthcare access. According to Perez “I immigrated to the United States
because of my family”. Also, John in answering one of the follow-up questions about why
he migrated to the United States said the decision to migrate was family decision and they
moved here because of jobs availability. He answered “No, I would not but healthcare

138
insurance is better here. We came here because of availability of jobs.” Finally, Juliana
also stated that she migrated to the United States to find better job, earn good income to
take care of the family. According to the U.S. DHS (n.d.) the primary driver of
immigration to the United States is the availability of jobs opportunities and family
reunion.
Summary
The main research question is, what are the lived experiences of formerly
undocumented Mexican immigrants living in Hidalgo County, Texas, regarding the role of
healthcare in their decision to migrate to the United States? The main purpose of the
research question is for me to explore the lived experiences of participants about the
problems of healthcare access in Mexico motivating them to immigrate to the United
States to access quality healthcare. To explore those experiences, I composed a
semistructured interview script, conducted interviews, and analyzed the data to discover
emerging themes.
In responding to the question about problems with health insurance in Mexico,
participants mentioned embezzlement of public health resources for personal gains, lack
of healthcare facilities at the rural areas, lack of doctors, and pay before care as major
challenges. And in responding to the question about the healthcare benefits in the United
State which could serve as pull factors, the participants mentioned the perception of free
healthcare access in emergencies, cheaper health insurance for undocumented immigrants,
and quality healthcare services. He explained why people moved from an area or location
to different place. The results from the analysis explained healthcare reasons some of the

139
participants migrated from Mexico to United States. However, the primary leading factors
for immigration to the United States are availability of jobs in the
United States and reuniting with families.
Chapter 5: Discussion, Conclusions, and Recommendation
Introduction
The study’s purpose was to understand the role of healthcare quality in Mexico in
undocumented immigration to the United States. I used a phenomenological approach to
explore detailed and in-depth information from the research participants on how
challenges or problems of health insurance in Mexico could encourage some Mexicans to
cross to the United States to benefit from a free or lower cost of health care. My
conceptual framework is situated on Lee’s push/pull theory. The study’s focus was to
collect data from formerly undocumented immigrant from Mexico to understand
healthcare access challenges in Mexico that motivated them to enter United States as
undocumented immigrants.
The study’s key findings about challenges of healthcare access in Mexico include
embezzlement public health resources, payment before treatment, lack of healthcare
facilities at the rural areas, and lack of doctors in public hospitals. The key findings about
healthcare reasons which motivated some participants to migrated include a perception of
free access to healthcare in emergencies, cheaper health insurance for undocumented
compared to documented due to charity and other U.S. government funded programs, and
quality healthcare services. The key findings align with Lee’s push/pull theoretical
framework.

140
Interpretation of the Findings
The main research question is what are the lived experiences of formerly
undocumented Mexican immigrants living in Hidalgo County, Texas, regarding the role of
healthcare in their decision to migrate to the United States? I used two main interview
questions to explore the research question. One main interview question was focused to
explore problems of healthcare access in Mexico. The other question centered on the
benefits of healthcare in the United States that motivate undocumented immigrants to
immigrate to the United States from Mexico. Interpretations of the findings for these
questions and the literature reviewed in Chapter 2 are discussed below.
First, most of the research participants (5 of 7) stated that payment in cash before
receiving medical services is a challenge to healthcare access in Mexico especially among
the poor. The literature reviewed in Chapter 2 about healthcare access in Mexico
confirmed this finding. Martinez-Martinez and Rodriguez-Brito (2020) stated that Mexico
has one of the highest out-of-pocket healthcare expenses among the countries belonging to
the Organization for Economic Co-operation and Development and some doctors
requiring patients to make payments before being attended to. This makes it harder for the
poor and vulnerable to access healthcare in Mexico. To support this Pelcastre-Villauerte et
al. (2017), mentioned that in Mexico, 73% of the population live below poverty and face
challenges to get insured or pay their medical bills. Also, all the participants have
identified corruption and embezzlement of public resources as another problem for
providing quality healthcare for people in Mexico. This is confirmed in the literature
reviewed as Hone and Gómez-Dantés (2019), Rivera-Hernández et al. (2019), and Sosa

141
and Sosa-Rubi (2016) contended that presence of corruption and mismanagement of
public resources in Mexico is a key challenge to provide and expand healthcare access to
the people.
Additionally, the findings revealed that lack of healthcare facilities in rural areas in
Mexico makes it difficult for the people living in these areas to access quality healthcare.
Most of the participants shared their long travel experiences to find hospital or clinic. The
lack of healthcare facilities in rural areas is confirmed by the literature reviewed.
According to Hone and Gómez-Dantés (2019), Rivera-Hernández et al. (2019), and Sosa
and Sosa-Rubi (2016) lack of healthcare facilities in the rural areas has denied many
people especially in rural areas to accessible quality healthcare in Mexico. Finally, on the
problems of healthcare access in Mexico, majority of the research respondents identified
lack of doctors in the public hospitals. Each of those participants explained how lack of
doctors affected them in Mexico. As reviewed in Chapter 2, Hone and Gómez-Dantés,
Rivera-Hernández et al., and Sosa and Sosa-Rubi collaborated on lack of healthcare
personnel and doctors as a challenge to addressing inequities of healthcare access in
Mexico.
To begin with, my study’s findings revealed that majority of the research
participants immigrated to the United States because they had a perception that they are
entitle to free healthcare services in emergencies, despite this fact being untrue for the
providers of those healthcare services. According to my findings, participants had
information and beliefs that during emergency situations doctors in U.S. hospitals and

142
clinics are required by the federal law to treat patients regardless of their background or
immigration status. This finding coincided with the literature reviewed. Kuruvilla and
Raghavan (2014) clearly stated that hospitals that receive federal funding in the United
States must screen and stabilize patients who need emergency care for free regardless of
their immigration status and ability to pay. Emergency care is backed by EMTALA, which
was first signed into law in 1986. Castaneda (2016) stated that in many large medical
schools, medical students provide free health care to the poor including undocumented
immigrants as part of their training rotations. However, according to Sawyer (2017), the
perceived “free” care is never free to the provider. American College of Emergency
Physicians (n.d.) added that emergency physicians on average provide $138,300 of
EMTALA charity care each year and incur on average $25,000 EMTALArelated-bad debt
in 2001 per the research conducted by American Medical Association (AMA) in May
2003. Further, the American Hospital Association (2021, February 28) has estimated that
approximately $660 billion dollars in the past 20 years has been spent in EMTALA and
other unfunded care resulting in upwards shifts of pricing to cover costs directly
impacting consumers and business alike.
The findings also revealed that healthcare insurance is cheaper for undocumented
immigrants in the United States. Some of respondents shared their experiences of
acquiring lower-cost health insurance from some community healthcare services and
nonprofit organizations. This information is confirmed by the literature in Chapter 2.
According to the literature some community health facilities, churches, and non-profit
organizations help undocumented immigrants to get health insurance at lower cost

143
(Artiga & Diaz, 2019; Castaneda, 2016; Flavin et al., 2018; Kuruvilla & Raghavan, 2014).
Also as already stated, in some larger medical schools’ medical students provide free
medical services to the vulnerable including undocumented immigrants (Castaneda,
2016).
Finally, some of the participants also mentioned that the healthcare services in the
United States are of higher quality than services provided in Mexico. They explained that
United States has better medical equipment and specialized doctors than Mexico. And this
has influenced their decision to move to the United States. This finding is not confirmed
by the literature reviewed.
By and large, these findings are aligned with the conceptual framework for this
study (Lee’s push/pull theory). Lee articulated that migration is caused by both push and
pull factors with intervening obstacles (Lee, 1966). The push factors according to the
findings are the challenges for healthcare access in Mexico. They are: (a) payments are
made before treatment, (b) corruption or embezzlement of public resources for personal
gains, (c) lack of healthcare facilities, and (d) lack of personnel or doctors in public
hospitals. The pull factors according to the findings are conditions in the United States
that promote access to quality healthcare to undocumented immigrants. They are: (a)
perceptions of free access to healthcare in emergencies, (b) cheaper health insurance for
undocumented immigrants, and (c) more quality healthcare services. The intervening
obstacles included hunger and fear of being shot or arrested.

144
Limitations of the Study
One of the study limitations is that majority of the interviews were not audio
recorded. This might have affected the quality of data collected, due to the difficulty
presented by listening to participants and taking notes simultaneously during interviews
(Ravitch & Carl, 2016; Rubin & Rubin, 2012). Secondly, I used a nonprobability
sampling technique to select the research participants. This technique, according to
Ravitch and Carl (2016), lacks randomness and enhances potential researcher. However,
Moustakas (1994) argued that the nonprobability technique can be used in qualitative
research because qualitative research focuses on discovering and providing in-depth
information on a topic to provide a better understanding but not how often something
happens. In addressing this, I used a nonprobability, convenient purposive sampling to
explore detailed and in-depth data. I also used triangulation, peer debriefing, and
bracketing strategies to check my personal bias to strengthen the credibility and
trustworthiness of the research findings. Finally, I used member checking technique to
double check and confirm answers participants provided to ensure the answers captured
were the correct answers participants wanted to provide to achieve data credibility.
Recommendations
There are two recommendations that emerged. The study was only conducted in
Hidalgo County, Texas. The study can be replicated in other neighboring counties and
states to study the overall impact healthcare benefits have on undocumented immigration
to the United States. According to the literature reviewed in Chapter 2, California is the
first state in the United States to provide state government-subsidized health benefits to

145
young undocumented immigrants (Allyn, 2019). This is an avenue for future research.
Another possible research area in the future is to widen scope of the study to include other
countries such as El Salvador, Cuba, East Africa, and West Africa as number of
immigrants in those areas keep increasing (Justice for Migrants, 2017 & Murtaza, 2020).
Implications
Finding ways to identify challenges for healthcare access in Mexico, the findings
will enlighten people about the role of healthcare in Mexico as a push for undocumented
immigration to the United Sates. The findings will also have positive implications for
social change in the field of public policy since it will add to our understanding of the
relationship between healthcare and immigration. It will also provide useful information
to the Hidalgo County local health department officials and United States Immigration
policy setters to better guide their debate and policies on healthcare policy. Also, the U.S.
Government needs to spend more time and resources to disabuse persons of the
information that emergency healthcare is “free”. The findings also revealed that the
primary factors leading of immigration to the United States are jobs availability and
reuniting with families and this information should help guide policies and debate on
immigration.
Conclusion
The study’s purpose was designed to understand the role of healthcare quality in
Mexico in undocumented immigration to the United States. The main research focused on
exploring the lived experiences of formerly undocumented Mexican immigrants living in
Hidalgo County, Texas, United States. A phenomenological approach was used. A

146
convenient non-probability sampling techniques was used to select all the research
participants. The conceptual framework was Lee’s push/pull theory of migration.
Based on the findings, majority of the research participants stated they moved to
the United States as undocumented immigrants to access quality healthcare. The research
findings are in line with Lee’s push factors of migration as the healthcare challenges in
Mexico served as the push factors. There are (a) payments are made before treatment, (b)
corruption or embezzlement of public resources for personal gains, (c) lack of healthcare
facilities, and (d) lack of personnel or doctors in public hospitals. The study’s findings on
Lee’s pull factors for the participants migration to the United States include (a) a
perception of free access to healthcare in emergencies, (b) cheaper health insurance for
undocumented immigrants, and (c) quality healthcare services. The implication of the
findings for social change is to enlighten us about the relationship between healthcare
access and migration and provide useful information for Hidalgo County local health
authorities and United States Immigration policy setters to better guide debate on public
healthcare policies. The U.S. government would be well served to spend time to clear
some misconception that emergency healthcare is “free”. Finally, the information that
availability of jobs and family reunion as primary pull factors of immigration to the
United Sates should be used by immigration legislators in the United States to help guide
debate on immigration policies.
Healthcare access in Mexico over a decade has faced some challenges. According
to Pelcastre-Villauerte et al. (2017), 73% of the population in Mexico live below the
poverty line of $10 a day and consequently, they are unable to purchase private health

147
insurance. The provision of healthcare services in Mexico can be acquired through public
or private insurance, but most of the services are provided under Popular Insurance,
known in Spanish as Seguro Popular (S.P.; Hone & Gómez-Dantés, 2019;
MartinezMartinez & Rodriguez, 2020; Sosa & Sosa-Rubi, 2016).
In May 2003, the government of Mexico established the S.P. to extend quality
healthcare insurance to the poor, under-insured, and uninsured, to address inequities in
quality healthcare access. Unfortunately, the program failed, and many people still lack
health insurance and quality health care services (Hone & Gómez-Dantés, 2019; Sosa &
Sosa-Rubi, 2016). Only 42.2% of the poor who lack permanent jobs are covered by the
S.P. health insurance in Mexico (Martinez-Martinez & Rodriguez, 2020).
The findings of my study will shed light and provide more information on the role of
healthcare in Mexico in undocumented immigration to the United States. The findings of
this study can have positive implications in the field of public policy, because it will add
to our understanding of the relationship between healthcare and immigration and provide
useful information to better guide the debate on healthcare policy. The findings of my
study will also reveal how healthcare access in the United States motivates some people
from Mexico to immigrate to the United States in an undocumented status to have access
to quality healthcare. This information will open a new door for further research on how
quality healthcare in the United States can cause undocumented immigration. In this
chapter, I provide an overview of the work by highlighting the background of the study,
the problem statement and purpose, and research questions. I also present the theoretical

148
foundation of the study, the nature of the study, and its limitations. Finally, I conclude the
chapter with a discussion of the potential significance of the study.
Background of the Study
Inés Ospina (2019), Macías-Rojas (2018), Orrenius and Zavodny (2019), and
Roberts (2017) explained that undocumented immigration had become a major political,
social, and economic problem in the United States over the decade. According to Heslin
(2018) and Hoekstra and Orozco-Aleman (2017), approximately 12 million
undocumented immigrants are living in the United States, making it difficult for the
government to track the population and implement social intervention policies.
Access to quality healthcare is a problem in Mexico. Pelcastre-Villauerte et al.
(2018), Guerra et al. (2018), Hone and Gómez-Dantés (2019), Martinez-Martinez and
Rodriguez (2020), Sosa and Sosa-Rubi (2016) explained that about 55% of the population
in Mexico lack access to quality healthcare insurance even after the implementation of the
S.P. program. According to Sosa and Sosa-Rubi and Hone and
Gómez-Dantés, healthcare access in Mexico increased because of the implementation of
S.P however, there remains several people who are uninsured or underinsured because of
lack of financial resources and effective management of the S.P. by the government. My
study will explore the role of healthcare in Mexico in undocumented immigration to the
United States. It will provide in-depth information on lived experiences of undocumented
immigrants to better understand the role of healthcare in undocumented immigration to
the United States. Also, this information can better guide debates on healthcare public
policies.

149
Problem Statement
In the United States, undocumented immigration has been a major social and
political problem (Robert, 2017). Historically, the long border between United States and
Mexico has been the focus of American government in curbing undocumented
immigration (Inés Ospina, 2019). Nearly 11 million undocumented immigrants are living
in the United States (Heslin, 2018; Hoekstra & Orozco-Aleman, 2017). According to
Passel and Cohn (2019), in 2017, there were 10.5 million undocumented immigrants in
the United States, including 4.9 million Mexicans (47 %), marking the first time that
undocumented immigrants from Mexico fell below half of the total undocumented
immigrants (Passel & Cohn, 2019). There are many reasons people immigrate to the
United States. According to Macías-Rojas (2018) and Robert (2017), the primary reasons
people immigrate to the United States include: employment, fleeing political persecution,
reuniting with family, and the desire to live in a free society.
Due to the social, political, and economic issues, such as an abundance of narcotic
drugs, pressure on social programs, and pressure on jobs associated with undocumented
immigration, Congress, in 1996, passed the Illegal Immigration Reform and Immigrant
Responsibility Act (IIRIRA) to reduce the undocumented immigration (Macías-Rojas,
2018). The probability rate of arrest and apprehension of undocumented immigrants has
increased from 40% in 2000 to 55% by 2015; approximately 304,000 undocumented
immigrants were apprehended along the U.S.-Mexican border in the 2017 fiscal year
(Orrenius & Zavodny, 2019). Another effect of undocumented immigration is that

150
American citizens are divided on the issue of undocumented immigration and the
divisions are along party lines (Robert, 2017).
The nature of health insurance in Mexico and its challenges, such as being
expensive, lack of quality healthcare services, and inaccessibility, have been recently
studied (Hone & Gómez-Dantés, 2019; Martinez-Martinez & Rodriguez-Brito, 2020;
Rivera-Hernández et al., 2019; Sosa & Sosa-Rubi, 2016). There is an existing body of
information on healthcare in Mexico, but that research does not significantly focus on
ineffective health insurance in Mexico and its relation to undocumented immigration in
the United States. This study will fill this gap by contributing to the body of information
needed to address the problem by providing an evidence-based approach to inform public
policy.
According to Pelcastre-Villauerte et al. (2017), in Mexico, 73% of the population
live below the poverty line and face challenges in purchasing private insurance. The
provision of healthcare services in Mexico can be acquired through public or private
insurance, but most of the services are provided under S.P. (Hone & Gómez-Dantés, 2019;
Martinez-Martinez & Rodriguez, 2020; Sosa & Sosa-Rubi, 2016). In May 2003, the
government of Mexico established the S.P. to extend quality healthcare insurance to the
poor, under-insured, and uninsured, to address inequities in quality healthcare access. This
was done through the 1983 amendment of Article 4 of the Mexican Constitution to
provide universal health care for every citizen (Guerra et al., 2018). Unfortunately, the
program failed, and many people still lack health insurance and quality health care
services (Hone & Gómez-Dantés, 2019; Sosa & Sosa-Rubi, 2016).

151
Only 42.2% of citizens that lack permanent jobs are covered by the S.P. health
insurance in Mexico (Martinez-Martinez & Rodriguez, 2020). The Mexican Institute of
Social Security (IMSS), which provides health insurance for only private companies’
employees, only covered 36.4% of eligible enrollees as many of them wanted to move to
S.P., which is relatively cheaper than the IMSS (Guerra et al., 2018; Martinez-Martinez &
Rodriguez-Brito, 2020). Although there exists evidence that S.P. has increased health
insurance coverage among the underserved, Mexico has one of the highest out-of-pocket
healthcare expenses among the countries belonging to the Organization for Economic Co-
operation and Development (Martinez-Martinez & Rodriguez-Brito, 2020). Despite the
improvement in healthcare insurance, inequities in healthcare provision and utilization
still exist because of lack of finance, personnel, and bureaucracy of the government (Hone
& Gómez-Dantés, 2019; Rivera-Hernández et al., 2019; Sosa & Sosa-
Rubi, 2016).
According to Artiga and Diaz (2019), Castaneda (2016), and Kuruvilla and
Raghavan (2014), even though undocumented immigrants in the United States are denied
healthcare from the Affordable Care Act (ACA) they may obtain low-cost care through
community health centers and hospitals that receive federal funding and are required to
screen and stabilize patients who need emergency care, regardless of their immigration
status. Emergency care is backed by the Emergency Medical Treatment and Active Labor
Act (EMTALA) which was first signed into law in 1986 (Kuruvilla & Raghavan, 2014).
Also, in many large medical schools, medical students provide free health care to
members of underserved communities, including undocumented immigrants, as part of

152
their training rotations (Castaneda, 2016). All these benefits may encourage some
Mexicans to embark on undocumented U.S. immigration to access free or lower-cost
quality health care for themselves and their children. Therefore, it is important to address
Mexico’s inaccessible health insurance to reduce the desire to participate in
undocumented immigration for the purpose to access free or lower-cost U.S. health care.
Purpose of the Study
The purpose of this qualitative study was to understand the role of healthcare
quality in Mexico in undocumented immigration to the United States. I used a
phenomenological approach to engage immigrants from Mexico to explore detailed and
in-depth information on how challenges or problems of health insurance in Mexico could
encourage some Mexicans to cross to the United States to benefit from a free or lower cost
of health care.
I recruited participants who were legal permanent residents and citizens of the
United States but focused on their healthcare access experiences both in Mexico and the
United States before they became legal residents. Smart phone interview was used to
obtain primary data from the participants using principles of confidentiality to protect
their welfare. The respondents were selected by using a convenient purposive sampling
strategy (see O’Sullivan et al., 2017; Ravitch & Carl, 2016). My study will include
persons residing in Hidalgo County, Texas.

153
Research Question
My study intended to answer the following principal research question: What are
the lived experiences of formerly undocumented Mexican immigrants living in Hidalgo
County, Texas, regarding the role of healthcare in their decision to migrate to the United
States?
Conceptual Framework
Lee’s (1996) push and pull theory of migration served as my conceptual
framework. According to Lee, social migration is premised on the push and pull factors
with intervening obstacles in the middle. For the push factors, Lee referred to undesirable
conditions such as poor healthcare, poverty, fear of political persecution, and famine that
force people to leave their homes for other places. The pull factors are conditions such as
good health, peace, good jobs, and prosperity that induce, motivate, and attract people to
places (Lee, 1996). While the push factors are associated with the place of origin, the pull
factors are related to the place of the destination. Lee stated that the decision of a person
to migrate is based on four factors: (a) push factors associated with the area of origin, (b)
pull factors associate with the area of destination, (c) intervening obstacles, and (d)
personal reasons (Lee, 1996). Lee’s push and pull theory of migration is suitable for this
study because it focuses on problems of healthcare insurance in Mexico encouraging
people to enter the United States as undocumented to have access to free or lower-cost
quality healthcare services.
The challenges of health insurance in Mexico may be seen as the push factors and
the free and lower cost of healthcare services for undocumented immigrants in the United
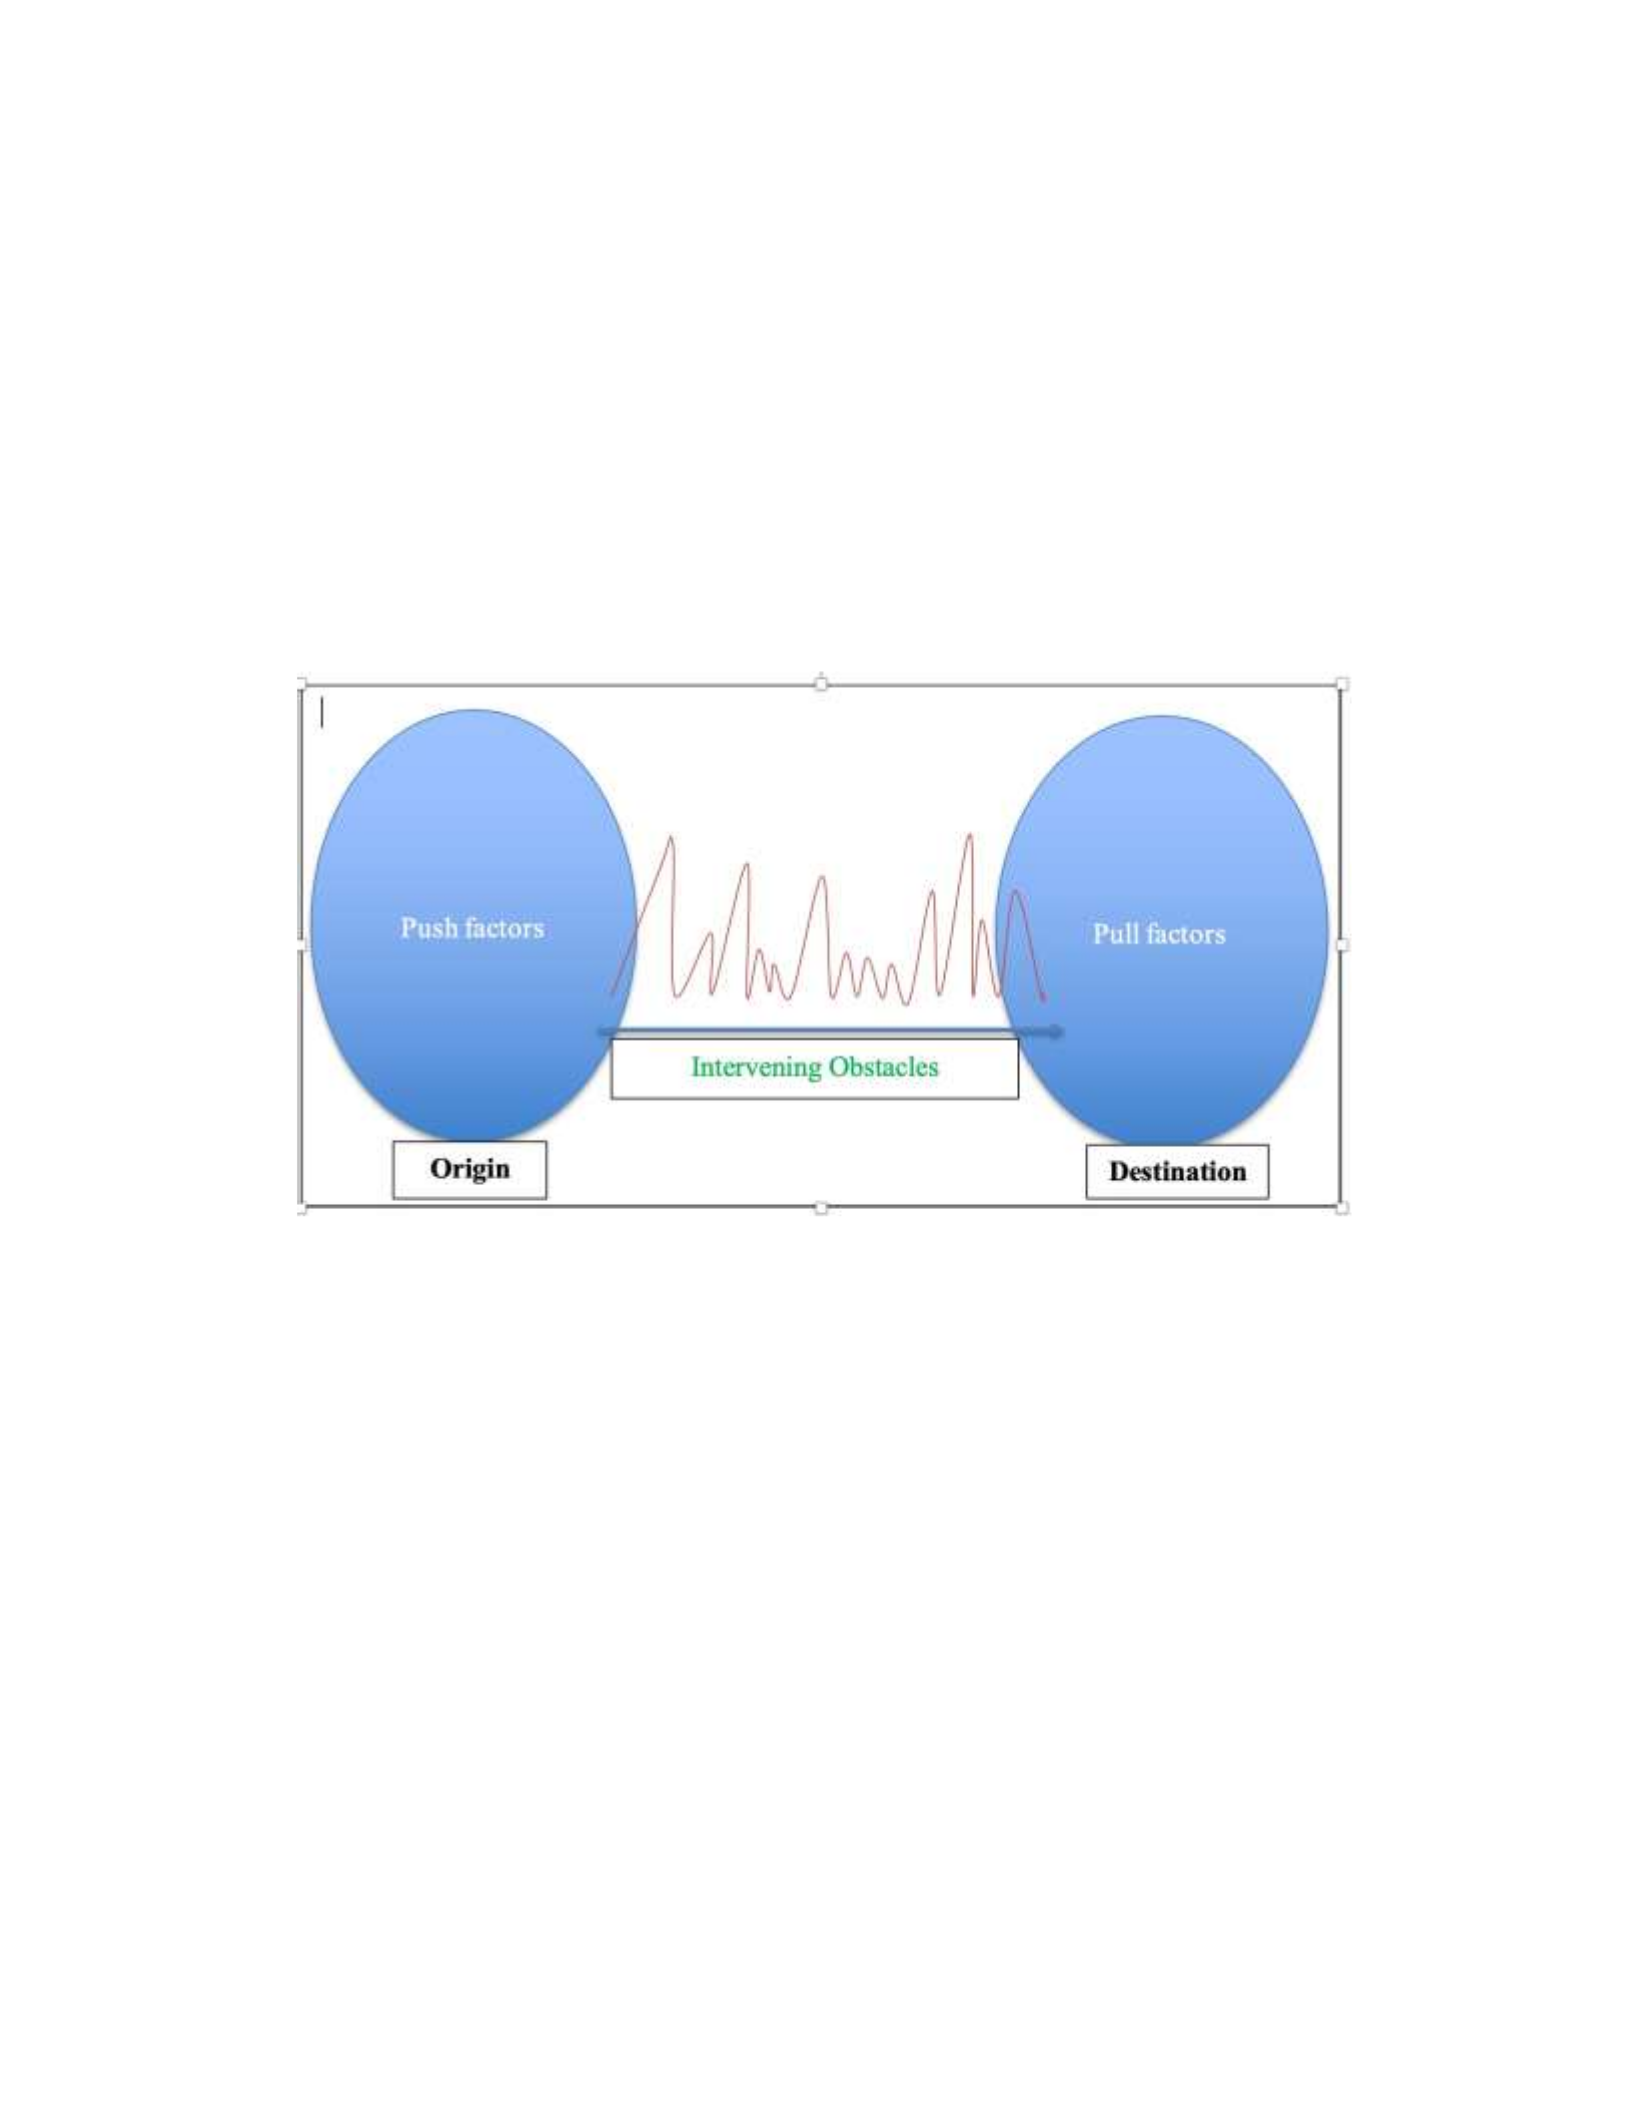
154
States through limited government programs may be seen as the pull factors as explained
in Lee’s theory. The intervening obstacles may refer to border security, distance, and
transportation challenges. The personal factors refer to the individual perceptions of both
the push and pull factors. Figure1presents the Lee’s model of migration.
Figure 1
Lee’s Model of Migration
Note. The model explains push factors as undesirable conditions at the original place that
discourages people to live there while pull factors at the destination motivate people to
move there. The intervening obstacles are conditions people experience or face during
movement from place of origin to destination.
Nature of the Study
My study used a phenomenological approach to examine the “lived experiences”
of migrants who experienced ineffective health insurance in Mexico, leading to
undocumented immigration to the United States. The study included the recruitment of
eligible participants in the United States.

155
Definitions
Affordable Care Act (ACA): It is officially knowns as Patient Protection and
Affordable Care Act, was passed into law in 2010 to expand the quality and affordable
healthcare to the uninsured and underinsured to promote healthcare accessibility
(Kuruvilla & Raghavan, 2014).
Emergency Medical Treatment and Labor Act (EMTALA): The Act was signed in
1986 stating that patients in emergency rooms must be treated regardless of their legal
status, insurance status, or ability to pay (Kuruvilla & Raghavan, 2014).
Immigration: It is the process through which a person or persons become
permanent residents or citizens of a different country (Parry, 2019).
Migration: It is the movement of people from one location to a particular location
because of push and pulls factors (Lee, 1996).
Push factors: These are issues that impel an individual to emigrate from his/her
country to a different country (Lee, 1996).
Pull factors: These are conditions that motivate a person to migrate to a different
location.
Undocumented immigrants: They are foreign-born individuals living in the United
States without authorization (Artiga & Diaz, 2019).
Assumptions
It is assumed that all research participants will participate willingly and honestly.
Another assumption is that all the participants have experienced challenges related to
health insurance in Mexico before becoming undocumented immigrants in the United

156
States. Participant confidentiality will be assured through the informed consent process
and interview design; therefore, it is assumed all participants will answer questions
truthfully. Finally, based on my background as an immigrant from Africa, I might be
biased in reporting some of the findings, but with my professional background, I should
be able to eliminate personal biases from the findings.
Scope and Delimitations
I recruited participants who are now legal permanent residents and citizens of the
United States but will focus on their healthcare access experiences both in Mexico and the
United States before they become legal residents. This study focused on in-depth
interviews of 7 participants. The research results may not reflect the experiences of all
undocumented immigrants, but it is assumed that it will represent a representative sample
of the target populations’ experiences. Hall (2010) interviewed five homeless individuals
for a phenomenological study on homelessness, and the results of the interviews indicated
that participants’ perceptions and experiences represent the entire homeless population in
the United States.
My study’s main challenge was language barriers. The research participants are
Hispanic, and some can only speak Spanish; a language I do not speak. Therefore, an
interpreter was used for participants who spoke Spanish for successful interviews. Also,
the time and location for interviews may pose an inconvenience, which may affect the
quality of the interviews. Another significant concern was the protection of the welfare of
the research participants. The confidentiality of the sensitive information provided by the
participants is paramount and must be abided by. However, divulging confidential

157
information of the participants through collection and analysis of data may harm the
participants in many ways, including economic, social, and psychological crises. As such,
all data will be reported using participant pseudonyms and aggregated themes apart from
some identity-protected statements that may help to illuminate individual and collective
experiences. My study’s purpose and objectives will be explained to the respondents and
their informed consent form will be obtained. Also, the SARS-CoV-2 (COVID-19)
pandemic may impact participant schedules and appointments, which may affect the
study’s overall timeline. The final limitation is the transferability and dependability of the
research findings as the study is qualitative and employs a non-probability sampling
strategy.
Limitations
I used a phenomenological approach to explore the lived experiences of Mexican
immigrants on the role of quality healthcare in their undocumented immigration to the
United States. One of the study limitations will be the difficulty in ensuring transferability
and dependability of study findings. Even though Lincoln and Guba (1985) and Shenton
(2004) explained strategies to achieve transferability and dependability (generalizability)
for qualitative research, both admitted it is difficult compared to quantitative research.
Secondly, I decided to use a nonprobability sampling technique to select participants. This
technique, according to Ravitch and Carl (2016), lacks randomness and enhances the
biases of the researcher. However, Moustakas (1994) argued that the nonprobability
technique can be used in qualitative research because qualitative research focuses on
discovering and providing in-depth information on a topic to provide a better

158
understanding but not how often something happens. In addressing this, I used a
nonprobability purposive sampling to explore my topic. I also used triangulation, member
checking, and peer debriefing strategies
Significance
My study focused on the role of healthcare in Mexico in undocumented
immigration to the United States. The findings will enlighten people about the role of
healthcare in undocumented immigration to the United Sates. The findings will also have
positive implications for social change in the field of public policy since it will add to our
understanding of the relationship between healthcare and immigration and provide useful
information to better guide the debate on healthcare policy.
Summary
In Chapter 1, I presented the background of the topic. I also detailed the problem
statement, purpose, and nature of the study in this chapter. I concluded Chapter 1 by
outlining the research questions, presented the conceptual framework, explained some
technical terms and research assumptions, outlined the scope and limitations, and finally
discussed the significance. Chapter 2 contains an in-depth literature review on
undocumented immigration, healthcare challenges in Mexico, and the conceptual
framework. Chapter 2 also presents a literature review on the research method and
approach. In Chapter 3, I presented information on the design of the research, role of the
researcher, selection of research participants, and instrumentation. This chapter also
covered procedures for data collection, data analysis plan, ethical procedures, and issues
of trustworthiness.

159
Chapter 2: Literature Review
Introduction
My study focused on exploring the research question: What are the lived
experiences of formerly undocumented Mexican immigrants living in Hidalgo County,
Texas, regarding the role of healthcare in their decision to migrate to the United States?
This chapter presents an approach for reviewing the literature. It includes an outline of the
historical, philosophical, and theoretical perception that entails immigration,
undocumented immigration, migration, and healthcare. The review of the literature starts
with an overview of the historical account of immigration, its effects, and policies put in
place to reduce undocumented immigration. The second section will present scholarly
literature relating to healthcare and its challenges in Mexico as well as healthcare for
undocumented immigrants in the United States. This chapter will also include a review of
the literature regarding the conceptual framework for the study. The final section will
address the literature review related to the approach and methodology.
Literature Search Strategy
For an intensive understanding and illustration of the theoretical and abstract
frameworks of the topic matter, the following databases were conjointly utilized: EBSCO,
ProQuest, ERIC, Google Scholar, and Healthcare Periodicals. I used the following
keywords in the search: immigration, undocumented immigration, undocumented
immigration, migration, healthcare insurance, migration theories, and push-pull theory. I
used relevant information from research articles, dissertations, books, seminars, and
organizations websites and the scope of publication year ranges from 1985 to 2020.

160
Historical Account of Immigration
Immigration is the process of moving to a new country to reside there permanently
(Connor, 2013; Parry, 2019). People who moved to a new country are called immigrants,
but these persons are called emigrants from the old country they moved away permanently
(Conner, 2016). Connor (2016) stated that the United Nations (UN) estimated there to be
232 million international migrants in the world, which is slightly more than 3% of the
world’s population. This percentage would be estimated to represent the world’s fifth-
most populous country if all the world’s migrants were living in a single country (Connor
& López, 2016).
According to Massey (1999), the modern history of international migration can be
divided into four periods: (a) the mercantile period, from 1500 to 1800 in which
immigration was dominated by Europe as a result of colonization and economic growth;
(b) the industrial period, which began from early 1800 to 1925 when more than 48 million
persons left Europe to the Americas and Oceania with a concentration of 85% to five
countries [Argentina, Australia, Canada, New Zealand, and the United States], with the
United States receiving 60 % of the 85% immigrants; (c) period of limited migration,
occurring in the 1930s where the receiving countries, most notably the United States, had
passed restrictive immigration laws because of the Great Depression; and (d) the period of
postindustrial migration in the 1960s during which immigration became a global issue
where sending countries like United Kingdom, France, Sweden, Italy, and Portugal as well
as the United States witnessed an overflow of immigrants from the developing countries
into their boarders.

161
Another history of mass movement of people occurred in Cuba in 1980 and 1994
(Martinez et al., 2015). In 1980, because of political and economic pressure on Cubans,
about 10,000 Cubans invaded the Peruvian Embassy seeking asylum and the Cubans
responded by opening port of Mariel to persons wishing to leave the country (Martinez et
al., 2015. They took the opportunity to decongest the prisons by expelling imprisoned
homosexuals and other prisoners. As a result of this mass immigration, more than 125,000
Cuban refugees arrived in Miami, Florida. Again, in August 1994, about 35,000
Cuban fled to Florida following the rafter crisis (Martinez et al., 2015).
Immigration in the United States
The United States has more immigrants than any other country in the world
(Budiman, 2020; Connor & López, 2016). Between 1880 and 1910 about, 17 million
European immigrants entered United States (Parry, 2019). More than 1 million
immigrants arrive in the United States each year (Budiman, 2020). As of 2015, the UN
stated that the immigrant population in the United States is about 46.6 million (Budiman,
2020; Connor & López, 2016). This represents 19% of the international immigrants. The
immigrant population in the United States is nearly four times that of the world’s next
largest immigrant destination – Germany, with an estimated immigrant population of 12
million (Budiman, 2020; Connor & López, 2016). According to Budiman (2020), in 2020
immigrants constituted approximately 13.7% of the U.S. population, 4.8 % in 1970, with
one of the largest migrations in the late 1800’s to fuel the U.S. industrial age. It is
estimated in 1890 that14.8% of the U.S. population, 9.2 million people, were immigrants.

162
Budiman (2020) further explained that only 77% of the immigrants in the United
States have followed legal processes and the rest are undocumented. It is important to
stress that since the formation of the federal Refugee Resettlement Program by the
Refugee Act in 1980, about 3 million refugees have admitted into the United States, more
than any other country in the world (Budiman, 2020; Connor & López, 2016).
Where Do U.S. Immigrants come from?
The United States of America is being described as the land of immigrants
according to Massey (1999), Parry (2019), and Robert (2017). Every year, about 1 million
immigrants arrive in the United States from all parts of the world; Mexico, China, India,
Philippines, El Salvador, Europe, Canada, Caribbean, Middle East, North Africa, and sub-
Saharan Africa (Budiman, 2020; Connor & López, 2016; Massey, 1999). For the
estimated 46.6 million immigrants of the United States, Mexico is the highest sending
country. In 2018, about 11.2 million (25%) immigrants living in the United States were
from Mexico, 6% each from China and India, 4% from the Philippines, 13% from Europe
and Canada, 10% from the Caribbean, 8% from Central America, 7% from South
America, 4% from the Middle East and North Africa, and finally 5% came from
subSaharan Africa (Budiman, 2020). In recent years new immigrant arrivals in the United
States have declined due to increasing immigration controls (Budiman, 2020; Orrenius &
Zavodny, 2019).
Undocumented Immigration
Most people have immigrated to the United States legally, but some have settled in
the country without permission. According to Martinez et al (2015), the term

163
undocumented immigrant is applicable under the following conditions: (a) legally entered
the country but remained in the country after their visa or permit expired; (b) received
negative remarks on their refugee or asylee application but remained in the country; (c)
experienced changes in their socioeconomic position but could not renew residence permit
but remained in the country; (d) used fraudulent documentation to enter the country; and
(e) unlawfully entered the country. Many of these people were desperate for a job, a better
life, or family reunification (Artiga & Diaz, 2019; Macías-Rojas, 2018;
Parry, 2019)
Robert (2017) explained that undocumented immigration has been considered one
of the major social, economic, and political problems in the United States. According to
Robert, polls conducted over the last 15 years revealed most Americans believe that U.S.
borders are not secured, and that the federal government could do more to reduce
undocumented immigration. As a result of this perception, border security has remained
the most controversial focal point of concern in the United States (Inés Ospina, 2019;
Roberts, 2017).
Nearly 11 million undocumented immigrants live in the United States (Heslin,
2018; Hoekstra & Orozco-Aleman, 2017). Budiman (2020) stated that from 1990, the
population of undocumented immigrants increased from 3.5 million to a high record of
12.2 million in 2007. However, by 2017, Passel and Cohn (2019) estimated the
undocumented immigrant population had decreased by 1.7 million, accounting for 10.5
million of which 4.9 million were estimated to be Mexicans. This constitutes 47% of
undocumented immigrants from Mexico in 2017, the first time the undocumented

164
immigrants from Mexico fell below half of the total undocumented immigrants (Passel &
Cohn, 2019). Budiman added that the 10.5 million undocumented immigrant population
constituted 3.2% of the overall U.S. population in 2017. Between 2007 and 2017 there
was a decrease of the Mexican undocumented immigrants by 2 million leading to an
overall decline of the undocumented immigrants from 12.2 million to 10.5 million in the
United States (Budiman, 2020; Passel & Cohn, 2019).
U.S. Public Perception of Undocumented immigrants
According to Gramlich (2019), a survey was conducted in June 2018 to obtain
opinions about immigrants in the United States. In this survey, only 45% of Americans
said most immigrants are in the country legally, but 35% incorrectly said that most of the
immigrants are in the country in an undocumented status. In another survey conducted
before the 2018 midterm elections among registered voters who planned to vote for
Republican and Democratic Parties, 75% of registered voters who planned to vote for the
Republican candidate said undocumented immigration was a serious problem in the
country against 19% among voters who planned to support Democratic candidate
(Gramlich, 2019). Gramlich also stated that 69% of Republicans agreed that expanding
the wall along the U.S Mexican border is a major restrictive measure to reduce
undocumented immigration, but 70% of Democrats indicated that measure would not be
effective in reducing undocumented immigration.
Baranowski (2012) and Krogstad (2020) stated that 74% of U.S. adults said they
favor granting permanent legal status to immigrants who came to the United States as
undocumented. Baranowski added that a survey was conducted among 686 participants

165
about perceptions of undocumented immigrants from Mexico. The findings revealed that
Latinos have more positive attitudes towards undocumented immigrants than White
Americans. Also, participants with higher education endorsed respect for undocumented
immigrants from Mexico more compared to participants with lower or without education
(Baranowski, 2012). Finally, participants who live within 200 miles of the U.S.- Mexican
border have less tolerant attitudes towards undocumented immigrants from Mexico than
participants who live far away from that region.
Effects of Immigration
There has an overwhelming pressure on healthcare infrastructure in the United
States and one of the causes is the rapid growth of undocumented immigrants (Muschek,
2015). Muschek added that the U.S. federal government spent about $29 billion to take
care of undocumented immigrants in the 2010 fiscal year. Out of this expenditure, $10.7
billion was spent on providing healthcare for undocumented immigrants (Muschek,
2015).
Undocumented immigration has led to an increase in population and an
overwhelming pressure on social welfare programs in the United States (Macías-Rojas,
2018; Muschek, 2015; Orrenius & Zavodny, 2019). Kerwin (2018) stated that, between
1997 and 2018, the budget of the U.S. DHS has increased from $1.935 billion to $21.1
billion in efforts to enhance border security and control undocumented entries. This
spending, including expenditure on the healthcare of immigrant children, drains the
federal coffers (Kerwin, 2018). According to Rueben and Gault (2017), when all the costs

166
of public goods are distributed to everyone in the United States, immigrant adults are
estimated to be more dependent on state and local budgets than native adults. There was a
$2,950 gap difference in budget impact between immigrants and individuals born in the
United States between 2011and 2013.
Borjas (2019) mentioned that from 1990 to 2014 the U.S. Gross Domestic Product
(GDP) would have been 15% less without the contribution and hard work of immigrants.
Borjas further explained that when the immigrants’ population increases by 1%, the
economy of the United States grows by 1.15%. This means that an increase in
immigration has been seen as a great contributor to the economic growth in the United
States. In 2016, foreign-born alone constitutes 16.6% of the labor force in the United
States contributing meaningfully to generating national wealth and output (Borjas, 2019).
According to Desilver (2019), in 2014 27.6 million immigrants were present in the U.S.
workforce of 161.4 million and out of the 27.6 million immigrants, 19.6 million came to
the United States legally; an estimated 8 million are undocumented (Desilver, 2019).
Immigration has been considered as source labor for the United States. In 2014, 33% of
farmworkers were immigrants, 45% of private households were immigrants, and 36% of
the textile and manufacturing industries employed immigrants (Desilver, 2019).
Gubernskaya and Dreby (2017) added that, generally, family-based immigration has a
positive impact on the economy of the United States compared to negative effects.
Healthcare and Undocumented immigrants
Flavin et al. (2018) mentioned that 52% of people in the United States believe that
expenditure on immigrants’ healthcare is a great burden on the economy and 67% of the

167
public hold the belief that undocumented immigrants should not qualify for social services
including healthcare. In the light of this, federal policies have been put in place to deny
undocumented immigrants’ access to public healthcare insurance, Medicare, and Medicaid
(Artiga & Diaz, 2019; Castaneda, 2016; Flavin et al., 2018; Kuruvilla & Raghavan, 2014).
The ACA, which was enacted in March 2010 by Congress to expand access to quality
healthcare, categorically denied undocumented immigrants from being covered (Artiga &
Diaz, 2019; Castaneda, 2016; Flavin et al., 2018; Kuruvilla & Raghavan, 2014). However,
undocumented immigrants may obtain low-cost health care through community health
centers, and hospitals that receive federal funding must screen and stabilize patients who
need emergency care for free regardless of their immigration status. Emergency care is
backed by the Emergency Medical Treatment and Active Labor
Act (EMTALA) which was first signed into law in 1986 (Kuruvilla & Raghavan, 2014).
Also, in many large medical schools, medical students provide free health care to the poor
including undocumented immigrants as part of their training rotations (Castaneda,
2016).
Allyn (2019) stated that California is the first U.S. state to provide state
government-subsidized health benefits to young undocumented immigrants. California,
since 2016, has allowed children less than 18 years to benefit from state taxpayer-backed
healthcare regardless of their immigration status (Allyn, 2019). Allyn added that the
lowincome undocumented immigrants aged 25 or younger are being covered by
California’s
Medicaid program.

168
Recent Efforts to Prevent and Reduce Undocumented Immigration
Due to the sociopolitical and economic issues, such as an abundance of narcotic
drugs, pressure on social programs, and pressure on jobs associated with undocumented
immigration, Congress, in 1996, passed the Illegal Immigration Reform and Immigrant
Responsibility Act (IIRIRA) to prevent or reduce the undocumented immigration
(Macías-Rojas, 2018). Orrenius and Zavodny (2019) stated that about 304, 000
undocumented migrants were arrested along the U.S. – Mexican border in 2017. This is
the lowest rate of apprehension since 1971. Robert (2017) corroborated that successful
undocumented entries in the United States have been reduced by 90% between 2005 to
2015 (from 2 million to 200,000) as a result of enhancing border security ranging from
added personnel to fencing to motion camera detection and the use of aerial surveillance.
The campaign of President Trump during the 2016 elections focused on the
negative effects of immigration included safety, narcotic abundance, rape, and job
security, and called for the need to extend the U.S.-Mexican southern border (Pierce,
2019). According to Pierce (2019), many enforcement measures were undertaken by the
Trump Administration to reduce undocumented immigration included if not all: (a)
National Guard deployment to the U.S. – Mexican border. As of March 2019, about
2,100 National Guards troops were still stationed at the border; (b) on April 6, 2018, the
Trump Administration declared a zero-tolerance policy on undocumented immigration
resulting in thousands of children being separated from their families; (c) active-duty
military deployment to the border in October 2018; and (d) increasing border patrol

169
staffing. In January 2017, President Trump ordered hiring 5,000 additional Border Patrol
officers and by the end of 2018, there were 21,370 officers authorized by Congress
(Pierce, 2019).
On April 29, 2019, the Associated Press reported that Acting Defense Secretary
Shanahan instructed that additional 230 troops be deployed to the southern U.S.-Mexican
border to help Customs and Border Protection (CBP) officers intensify efforts to secure
the border against undocumented entries. This deployment, approved by the Acting
Defense Secretary Shanahan, cost the federal government an estimated $7.4 million. This
money could have been used to address other social and economic challenges (Pierce,
2019).
Healthcare
Baltagi et al. (2017) investigated a relationship between healthcare expenditure
and individual income among 167 countries between 1995 and 2012. Their findings
revealed that healthcare is an essential service rather than a luxury and that the prices of
healthcare services of countries depend on the level of the country’s income distribution.
Lower-income level countries tend to have a higher income elasticity of demand for
healthcare services (Baltagi et al., 2017). The cost of healthcare over the years has
increased in the United States and in developing countries alike deterring many people
from accessing healthcare.
During the 67th meeting of the UN General Assembly in New York, all
membercountries passed a resolution in support of universal healthcare systems (Hynes,
2013).

170
The tenets of the resolution emphasized and encouraged member-countries to provide and
deliver affordable and quality-driven healthcare services to all individuals to help to
achieve the UN Committee’s goals (Hynes, 2013). Hynes added that the resolution
directed member-states to roll out health care policies that do not require healthcare
consumers to pay for important medical services because expensive out-of-pocket
payments can deny poor people quality healthcare access. The UN Committee admitted
challenges facing universal healthcare accessibility but stated that universal healthcare is
worth pursuing as it is the foundation of sustainable development and a means for poverty
reduction. About 150 million people each year face difficulties to pay their medical bills
worldwide and many must sell their assets or go into debt to offset their healthcare bills
(Hynes, 2013).
Murtaza (2020) used the Lee’s push/pull model to explain that United States has
been on top in the world for receiving immigrants since 1970. The immigrants are
motivated to migrate to the United States because of availability of healthcare facilities,
services, and economic opportunities (International Organization for Migration, 2020;
Justice for Immigrant, n.d; Murtaza, 2020). Murtaza further explained that Mexico is the
second largest country of origin for immigrants after India. To collaborate Murtaza, the
report of IOM in 2020 stated that 11.8 million Mexicans migrated out of Mexico and 17.5
million Indians left for abroad in 2019. Using Lee’s push and pull theory, Murtaza
demonstrated that people migrated from different places like Africa, South America, and
Asia because of lack healthcare services and facilities to the United States for quality
healthcare services and better life.

171
Healthcare Access in Mexico
Many countries, including Mexico, still face challenges for ensuring universal
health coverage following the UN’s resolution and the Group of Twenty’s (G20)
declaration and commitment to providing universal health coverage (Hone &
GómezDantés, 2019). Mexico has been in the spotlight related to its effort to expand
quality universal healthcare among its citizens. Hone and Gómez-Dantés (2019),
Martinez-
Martinez and Rodriguez-Brito (2020), Rivera-Hernández et al (2019), and Sosa and Sosa-
Rubi (2016) identified these challenges to include difficulty in examining the term
“universal,” providing “quality healthcare” services, not just access, what type of medical
services to provide, lack of political consensus, and lack of resources. According to
Pelcastre-Villauerte et al. (2017), in Mexico, 73% of the population live below poverty
and face challenges to get insured.
According to Hone and Gómez-Dantés (2019), over the years, Mexico has been
advancing healthcare as a social right, expanding healthcare to the uninsured, and has
invested in infrastructure. The provision of healthcare services in Mexico can be acquired
through public or private insurance, but most of the services are provided under Popular
Insurance, known in Spanish as Seguro Popular (S.P.; Hone & Gómez-Dantés, 2019;
Martinez-Martinez & Rodriguez, 2020; Sosa & Sosa-Rubi, 2016). In May 2003, the
government of Mexico established the S.P. to extend quality healthcare insurance to the
poor, underinsured, and uninsured, to address inequities in quality healthcare access. This

172
was done in line with the 1983 Amendment of Article 4 of the Mexican Constitution to
provide universal health care for every citizen (Guerra et al., 2018).
Unfortunately, the program failed, and many people still lack health insurance and
access to quality health care services (Hone & Gómez-Dantés, 2019; Sosa & Sosa-Rubi,
2016). Only 42.2% of the poor that lack permanent jobs are covered by the S.P. health
insurance in Mexico (Martinez-Martinez & Rodriguez, 2020). The Mexican Institute of
Social Security (IMSS), which provides health insurance for only private companies’
employees, covered only 36.4% of eligible enrollees as many eligible enrollees sought to
be covered under S.P., which is relatively cheaper than the IMSS (Guerra et al., 2018;
Martinez-Martinez & Rodriguez-Brito, 2020). However, the S.P. is not resourceful to
insure them.
Although there exists evidence that S.P. has increased health insurance coverage
among the poor, Mexico has one of the highest out-of-pocket healthcare expenses among
the countries belonging to the Organization for Economic Co-operation and
Development (Martinez-Martinez & Rodriguez-Brito, 2020). Despite the improvement in
healthcare insurance, inequities in healthcare provision and utilization still exist because
of lack of resources, corruption, and inefficiency of the government (Hone & Gómez-
Dantés, 2019; Rivera-Hernández et al., 2019; Sosa & Sosa-Rubi, 2016). Lack of
resources, such as inadequate health personnel, finance, and healthcare facilities
especially in the rural areas have affected accessible healthcare in Mexico (Hone &
Gómez-Dantés, 2019; Rivera-Hernández et al., 2019; Sosa & Sosa-Rubi, 2016).

173
Conceptual Framework
Lee’s push and pull theory served as my research lens. Lee (1996) and Liang
(2006) stated that Ravenstein, who has been considered the originator of the theory of
migration and expert in a social movement, defined migration as moving from one
location to another location as a resident for pressing issues. There are two basic types of
migration; inter-migration (between countries) and intra-migration (within one country;
Lee, 1996; Waldinger et al., 2008). Waldinger et al. (2008) emphasized that the theory of
migration is broadly perceived on basis of international migration which is driven by a
country’s economy, healthcare, political, racial, and cultural identities, and tolerance.
Lee on April 23, 1965, at the Annual Meeting of Mississippi Valley Historical
Association, Kansas City, presented an academic paper on migration and why people
immigrate or emigrate (Lee, 1996). Lee explained that social migration is premised on the
push and pull factors with intervening obstacles in the middle. For the push factors, Lee
referred to undesirable conditions such as poor healthcare, poverty, fear of political
persecution, and famine that force people to leave their homes for other places. The pull
factors are conditions such as good health, peace, good jobs, and prosperity that induce,
motivate, and attract people to places (Lee, 1996). While the push factors are associated
with the place of origin, the pull factors are related to the place of the destination. Lee
stated that the decision of a person to migrate is based on four factors: (a) push factors
associated with the area of origin, (b) pull factors associate with the area of destination,
(c) intervening obstacles, and (d) personal reasons (Lee, 1996).

174
Murtaza (2020) investigated causes of international migration and used Lee’s push
and pull theory as a framework. In this work Murtaza mentioned availability of healthcare
services as a pull factor for migration to the United States and lack of quality healthcare
facilities as push factor. Wurie (2012) also used Lee’s push and pull model to demonstrate
reasons Latinos in Cuba, Mexico, and El Salvador came to the United States. Justice for
Immigrants (2017) also used Lee’s push and pull theory to illustrate the difference
between push and pull factors on international immigration. Faridi (2018) explained that
Lee’s theory of push/pull is one of the best models of theories of migration. Faridi added
that the push/pull theory examined causes of migration both at the place of origin and
destination. Faridi further implied that lack of healthcare services may push people out of
their places and available healthcare services attract immigrants as a pull factor. Justice for
Migrants (2017) illustrated how lack of healthcare services and availability of healthcare
services can serve as push and pull factors under Lee’s theory (See Figure 2).
Figure 2
Push/Pull Factors of Immigration
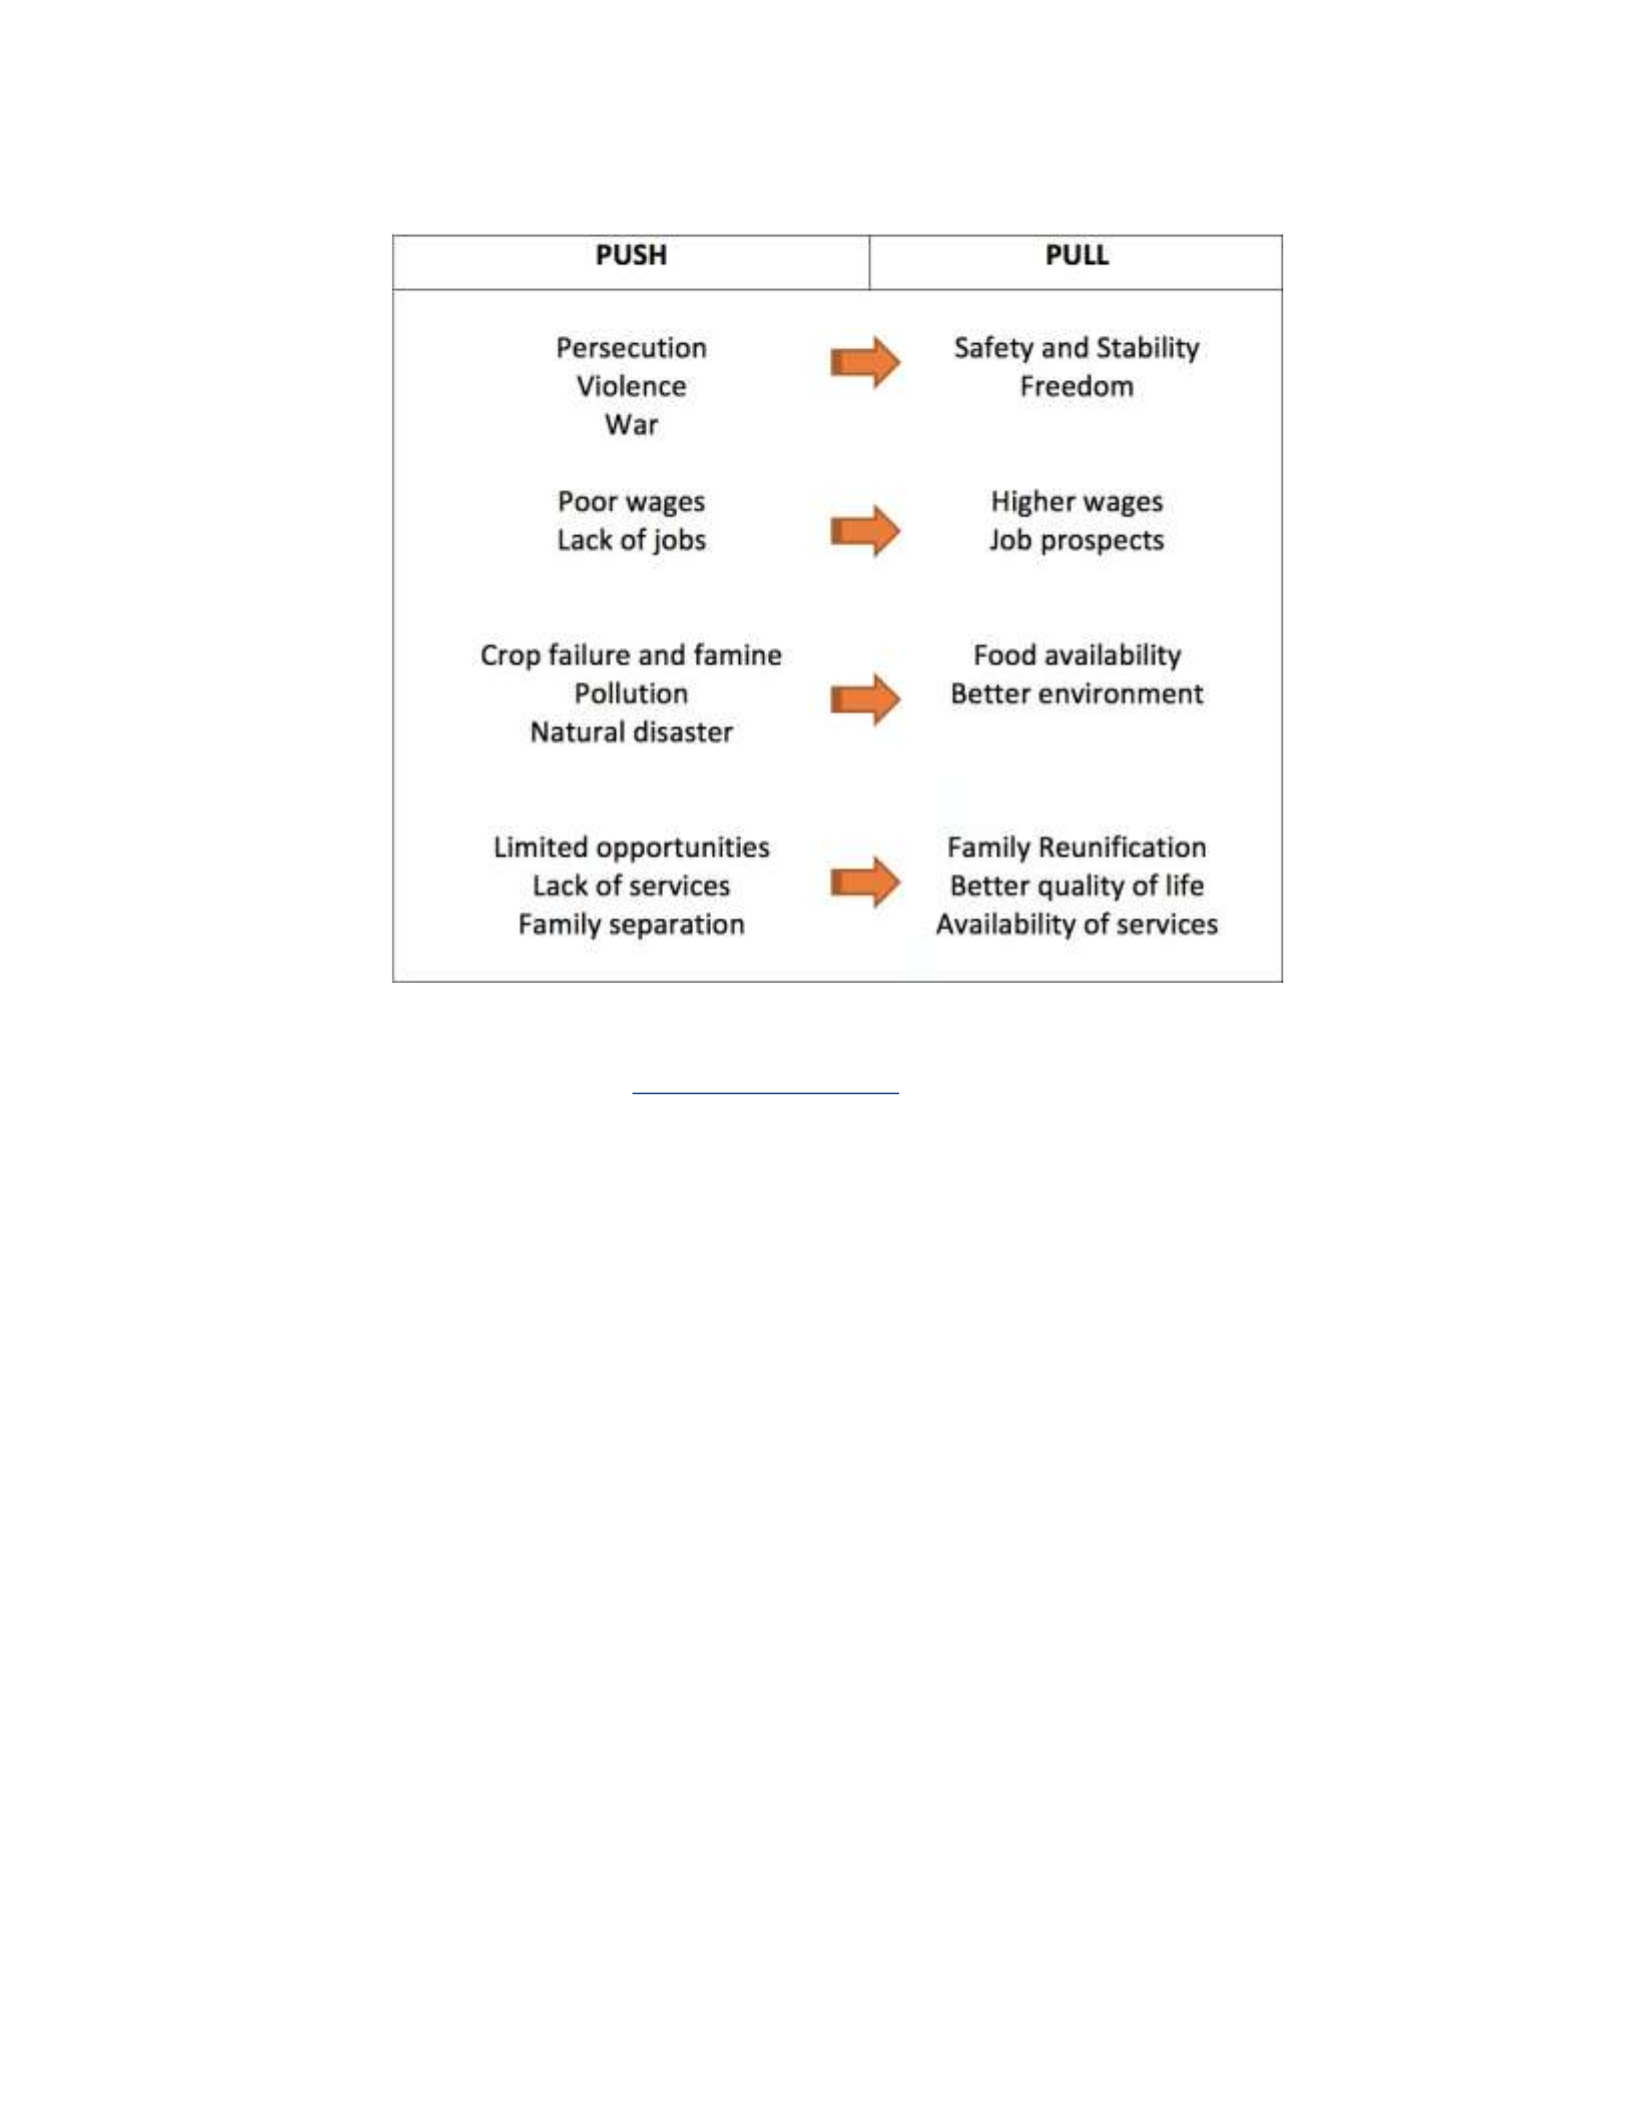
175
Note. Lack of services as push factors refers to lack of quality healthcare services and
facilities in original location. From “Root Causes of Migration” by Justice for
Immigration, 2017, https://justiceforimmigrants.org/what-we-are-
workingon/immigration/root-causes-of-migration/#_edn14. Public Domain.
Problems of accessing healthcare insurance in Mexico may be encouraging people
to enter the United States as undocumented immigrants to have access to free or lowercost
quality healthcare services. The challenges of health insurance in Mexico may be seen as
the push factors and the free and lower cost of healthcare services for undocumented
immigrants in the United States through limited government programs may be seen as the
pull factors as explained in Lee’s theory. The intervening obstacles may refer to border
security, distance, and transportation challenges. The personal factors refer to the
individual perceptions of both the push and pull factors.

176
Methodology and Approach
I employed a phenomenological approach to explore and examine lived experience
of the research participants on the quality of healthcare in Mexico in undocumented
immigration to the United States. According to Denzin and Lincoln (2008), Husserl was
considered the father of phenomenological approach because he used the approach to
conduct many research studies on the behavior and lived experiences of people.
Moustakas (1994) phenomenology research makes it possible for a researcher to actively
engage participants to explore lived experience on concerning social issues. Moustakas
further explained that under phenomenological research, a researcher should focus on
personal observations, participants’ experiences, and emotions to make meanings.
Phenomenological research also focuses on listening, documenting, and interpreting lived
experiences and behaviors in real life (Moustakas, 1994; Patton, 2015; Ravitch & Carl,
2016; Sloan & Bowe, 2014). Moustakas and Ravitch and Carl (2016) summarized
phenomenology characteristics to include: (a) focuses on meanings of lived experiences,
(b) aligns with qualitative research method, (c) does not predict relationships between
variables as in quantitative research, (d) the approach fully engages research participants
attention as they account their experiences, and (e) the approach focuses on meanings and
not how frequently an event occurs or is repeated.
Wurie (2012) conducted a qualitative study and used the phenomenology approach
with 7 participants. The study focused on exploring the lives of Salvadoran families after
the implementation of IIRIRA. This study is similar to my study as both focus on
exploring lived experience of a particular group of people (immigrants) in the United

177
States. While Wurie’s population was the Salvadoran community, mine will target the
Mexican immigrants in the United States. Hall (2010) employed a phenomenology
approach to understanding the challenges of homeless individuals towards
selfindependence. Hall also used this approach to elicit lived experience of homeless
people as I intend to use it to understand lived experience of immigrants on healthcare
insurance challenges in Mexico to undocumented immigration in the United States.
Finally, another important literature review on the approach is the work by Davis and Erez
(1998). These authors used a phenomenology approach to examine the lived experiences
of immigrants towards the multicultural criminal justice system in the United States. I
have the same reason to use the phenomenology approach as the authors, but the
difference is the target population. For these notions, I used a phenomenology approach to
provide in-depth accounts of Mexican immigrants on healthcare insurance challenges in
Mexico to undocumented immigration in the United States.
Summary and Conclusion
As articulated in chapter 2, undocumented immigration has been an issue in the
United States and nearly 11 million undocumented immigrants are living in the United
States making it difficult for the government to track the exact population. The growing
number of undocumented immigrants over the decades has put pressure on social service
and welfare programs and the inflow of narcotic drugs through the southern U.S.Mexican
border. This chapter presented a literature review on focused immigration patterns,
specifically undocumented immigration to the United States, and its effects and efforts
made to prevent or reduce undocumented immigration by the Trump

178
Administration.
This chapter also covered a literature review of healthcare insurance in Mexico
and its challenges. Lee’s push and pull theory served as my conceptual lens. The theory
posits that people begin to move to different places because of push and pull factors. Lee’s
push and pull theory is appropriate and aligns with the purpose of the study. The study
focused on exploring undocumented immigrants’ experience on the role of quality
healthcare in undocumented immigration to the United States. Chapter 3 contains
information describing my methodological approach to explore the lived experience of
undocumented U.S. immigrants. Chapter 3 outlines the research design, sample size,
processes for participant selection, instrumentation, the procedure for data collection,
plan for data analysis, ethical issues, and issues of trustworthiness.
Chapter 3: Research Methodology
Introduction
This study relied on a phenomenological research approach to elicit a detailed
lived experience of Mexican immigrants on problems of health insurance in Mexico as a
driver for undocumented immigration to the United States. I explored the lived
experiences of adults who have immigrated to the United Status in a previous
undocumented status to provide an in-depth look at information regarding healthcare
access as a driver for their immigration journey. This chapter elaborated on the research
questions, interview questions, qualitative methodology, role of the researcher, procedures
of data collection, ethical concerns, phenomenology inquiry, validity, reliability, and
conclusion.

179
Research Design and Rational
Research Question
The main research question was: What are the lived experiences of formerly
undocumented Mexican immigrants living in Hidalgo County, Texas, regarding the role of
healthcare in their decision to migrate to the United States?
Qualitative Method
I relied on a phenomenological design to investigate the lived experience of
Mexican immigrants on the role of health insurance problems in Mexico in relation to its
push factors for undocumented immigration to the United States. Denzin and Lincoln
(2009), O’Sullivan et al (2017), Patton (2015), and Ravitch and Carl (2016) opined that
phenomenological focuses on eliciting and interpreting lived experiences and narrations
while the quantitative method is appropriate for studies that focus on testing hypotheses to
understand causal relationships between variables or phenomena. O’Sullivan et al and
Ravitch and Carl did further explain that the choice of research method is determined by
the nature of the research question. If the research question is exploratory and seeks to
provide in-depth information about a problem, the appropriate research method is
qualitative (Denzin & Lincoln, 2009; O’Sullivan et al., 2017; Ravitch & Carl, 2016).
Based on this and the purpose of my research, the appropriate method I used is the
qualitative method.
Phenomenological Research
Phenomenology is one of the approaches of qualitative research. It focuses on
listening, documenting, and interpreting lived experiences and behaviors in real life

180
(Moustakas, 1994; Patton, 2015; Ravitch & Carl, 2016; Sloan & Bowe, 2014). According
to Denzin and Lincoln (2008), Husserl was considered the brainchild behind the
phenomenology approach as he used the approach to conduct research on the behavior
and experiences of people. Moustakas (1994) explained that under phenomenological
research, a researcher should focus on personal observations, participants’ experiences,
and emotions to make meanings. McNabb (2008) added that phenomenology is utilized in
social research to find social meanings of problems, activities, arts, and work. This has
justified my intention to use the approach to explore lived experiences of Mexican
immigrants on the role of healthcare quality in undocumented immigration to the United
States.
The Role of the Researcher
My interest is to involve communities in identifying social problems related to
healthcare and finding solutions to the problems through empirical inquiry. I used
interviews to elicit lived experiences of the research participants. My role in the process
was to recruit participants, interview them using a semistructured question list, listen and
record findings that conveyed their feelings and lived experiences in relation to the role of
healthcare insurance in Mexico in undocumented immigration to the United States.
Participant Selection
All participants reside in Hidalgo County, Texas, United States, and initial
recruitment was conducted using a social media platform in which I posted my research
interest in English and Spanish on my personal page seeking participants (see Appendix
A). The target population was legal immigrants from Mexico who entered the United

181
States in an undocumented immigrant status. I used a convenient purposive sampling
technique for recruitment. A convenient purposive technique allows the researcher to
select participants who are knowledgeable and have in-depth information about the topic
(Ravitch & Carl, 2016; Rubin & Rubin, 2012; Sharma, 2017). Individuals who responded
to either the English or Spanish social media recruitment posting were contacted using
direct messaging in the social media application and provided further contact details to
review study inclusion criteria and informed consenting procedures. Date and time
stamping were captured and chronologically utilized for participant selection in the event
the interest exceeds required participant threshold. If social media recruitment efforts
failed to achieve seven potential participants, I had planned to use a snowball recruitment
strategy to enlist additional participants by asking my participants who have completed
the study interview to inform other people about the study and provide them my contact
information or direct them to the social media posting for direct messaging. This snowball
recruitment strategy was not needed as I was able to recruit and retain all seven
participants during the initial recruitment process.
I used a sample size of seven participants. The justification for this can be seen in
the research work of Wurie (2012), where he used the same phenomenological research
and a convenient purposive sampling technique of a sample size of seven adults to
investigate the awareness of the implementation of 287(g) among Salvadoran immigrants
to explore the awareness of 287(g) policies among Salvadoran immigrants in the United
States. The similarity between my research and Wurie’s study is that I also used both
qualitative, phenomenological approach, and a convenient sampling strategy with seven

182
participants. Rudestam and Newton (2007) stated that a recommended sample size for
phenomenological research should range between five to 30 participants. According to
Creswell (2007) the recommended sample size for a phenomenological study is between
five to 25, as far as saturation is concerned. Saturation according to Mason (2010) is the
amount of quality information a researcher needs to provide a detailed and clearer picture
about a topic. Morse contends that a minimum of six participants are required for a
proper phenomenological study to be conducted (Mason, 2010). Therefore, my sample
size was seven participants. Another reason is that qualitative study focuses on credible in-
depth information, but not frequencies and generalizations (Mason, 2010; Ravitch &
Carl, 2016).
I understand the vulnerable nature and welfare of the participants. The
immigration legal status of the participants makes them vulnerable and revealing this
confidential information will subject them to possible legal suits, jail time, and
deportation. To protect and keep them safe, I will not reveal any information on their legal
status nor reveal any confidential information that may jeopardize participants’ welfare. I
will assign participant pseudonyms to conceal their identities.
Instrumentation
I used phone interviews to explore my research question. Smart phone and internet
platform interviews were conducted using a qualified Spanish interpreter for participants
wishing to conduct their interviews in Spanish. Using a three-way smartphone calling
feature, I initiated a call first with my Spanish interpreter and then add the participant to
the call. The participant was asked if they wish to conduct the interview in English or

183
Spanish. For those expressing their request to conduct in English, the Spanish interpreter
exited the group call. For those wishing to conduct the interview in Spanish, the interview
proceeded with the Spanish interpreter present. For interviews conducted using an
internet-based connection tool each attendee will be provided a conference access link to
join at the prearranged access time. Interviewing is one of the many ways to collect data
for qualitative studies (Jacob & Furgeson, 2012; Rubin & Rubin, 2012). Interviewing is
the most appropriate tool because my study uses a phenomenology method, which focuses
on exploring in-depth human experience with interest phenomenon (Patton, 2015). The
semistructured interview gives participants enough time and flexibility to expand their
answers and provide detailed information (Rubin & Rubin, 2012). It also allows the
researcher to ask probing or follow-up questions for clarity (Rubin & Rubin, 2012). On
these notions, I used a semistructured interview to explore my participants' lived
experiences and allow them to provide indepth information on the topic. But Ravitch and
Carl (2016) and Rubin and Rubin (2012) cautioned that researchers using semistructured
interviews should remain focused and take control of the process in line with the research
question. According to Jacob and Furgeson (2012), interviewing makes it possible for
participants to share their stories in detail for quality information.
I formulated my interview questions (see Appendix B) to align with my research
question based on the existing interview question from existing scales and studies and the
tips provided by Jacob and Furgeson (2012). I also reframed some focus group interview
questions of Betancourt et al. (2015) for Somali refugees to create the first, second, and
third questions. I also revised interview questions on accessible healthcare in Mexico

184
(Martinez-Martinez and Rodriguez-Brito,2020) to formulate question 2 and 3. I
formulated question 4, 5,6,7, and 8 based on Lee’s push and pull theory, the work of
Murtaza (2020), and Wurie (2012).
The first question of the interview questions intended to gather information about
the background of the respondents. Jacob and Furgeson (2012) explained that the
background questions help the researcher to warm up participants and facilitate the
selection process. The information I obtained help me to determine whether participants
have met selection criteria based on age and birthplace or country of origin. The second
and third questions dealt with accessibility of health insurance in Mexico and its
challenges. Question four covered the benefits of healthcare in the United States and how
they motivate immigrants as pull factors. The fifth question sought information about how
participants came to the United States because of cheaper and accessibility to healthcare.
The final question centered on the differences between health insurance accessibility in
Mexico and health insurance accessibility in the United States.
Interview questions should be open-ended and clear to understand (Ravitch &Carl,
2016; Rubin & Ruin, 2012). The questions should not be leading respondents to specific
responses, nor should clues about possible responses be embedded within them (Rubin &
Rubin, 2012). The construction of the interview questions should not contain words that
may trigger passions, inflate emotions, or disrespect respondents (Rubin & Rubin, 2012).
The other data sources I included are declassified information from the website of U.S.
DHS regarding undocumented immigration on the southern border. This created an

185
opportunity for triangulation of all the sources of data for valid and credible data
(Shenton, 2004).
Procedures for Data Collection
Following the recruitment process above, I emailed an informed consent in both
English and Spanish wherein the purpose of the research is explained in more detail to
include participants’ rights and the voluntary nature of their participation to include the
right to withdraw from the interviews at any time and the right to skip any question they
feel uncomfortable answering. Participants could schedule the interview for their
convenience after they agree to participate.
According to Rubin and Rubin (2012), recording and transcribing or taking notes
of interviews help the researcher minimizes biases and produces credible findings. I
sought permission to audio record and transcribe the interviews for credible data. I used
the Call Recorder smartphone application to digitally capture telephone interviews for
transcription. For interviews being conducted using internet connectivity tools, I used the
embedded recording features in the digital product to produce data transcripts. For
confidentiality purposes when using an internet-based connecting tool, participants were
advised that they may keep their video cameras off. For those participants who decline to
be audio recorded either during smartphone or interview-based connections, I took
detailed notes throughout the interview process. Participant pseudonyms are used for
confidentiality purpose.

186
Data Analysis Plan
I used the Call Recorder application to record and transcribe phone interviews and
I used embedded voice recording features of internet-based connection tools for
interviews conducted using these interfaces. I took interview notes for those sessions in
which audio recording was declined. Transcription of interviews helps the researcher to
have a vivid understanding of what transpired during interviews and captures exactly what
each participant says (Rubin & Rubin, 2012). Following transcription construction,
I used ATLAS.ti software for coding and data analyses. According to Rubin and Rubin
(2012), coding is one of the first key elements of qualitative data analysis and
interpretation. The ATLAS.ti software is one of the leading software qualitative data
analyses (QDA) tools and it provides researchers with a broad scope of informative
details related to their phenomenon of interest (Boston University, n.d; Predictive
Analysis Today, 2016a). ATLAS.ti also allows researchers to gain in depth information
and to see content patterns bringing meaning to information (Boston University, n.d;
Predictive Analysis Today, 2016a).
Ethical Consideration
My participants are considered vulnerable immigrants and, as such, issues of
privacy and confidentiality are very important. All participants are anticipated to be in a
legal U.S. resident status at the time of interviews. Participants may choose to discuss or
describe their immigration journey; however, I had not explored specific information
regarding immigration status in my interview questions. Informed consent was used to
describe participant rights. Creswell (2007) stated that a researcher should explain the

187
purpose of a study to participants to gain their trust. Participants were assigned
pseudonyms for confidentiality. To achieve this, I allowed participants to choose unique
alphabets other than their real names to conceal their identities. If the selected alphabet
has already been adopted by another participant in a concluded interview, I ask the present
interview participant to select another alphabet. Creswell added that the true names of
participants should not be used to enhance their privacy and confidentiality. I explained to
each participant my study’s purpose and remind them that participation is voluntary, and
any participant is free to quit at any stage of the investigation. According to Ravitch and
Carl (2016) and Rubin and Rubin (2012), it is unethical to lie to participants about a
study’s purpose or force any person to participate in research. My interview questions
were constructed as open-ended questions and were not expected to demean or trigger
respondent emotions. Data protection is the process of ensuring the security of
information obtained from participants to guarantee their safety (Rubin & Rubin, 2012) To
ensure data protection, I removed all information or cues on interview transcript that
might reveal participants’ identity. I only shared the redacted findings and analysis with
the Walden University’s faculty members. I securely stored the contact information of
participants, data, and study analyses on electronic files in Dropbox with a backup file
stored on an encrypted flash drive. I secured the flash drive in my locker I will keep and
protect the data for at least 5 years as required by Walden University. At the conclusion of
the required 5-year storage period, I will destroy electronic data using a disc wipe
software and all information contained on paper will be shredded.

188
Member Checking
I provided each participant an opportunity to member-check their transcriptions to
ensure information has been clearly captured and to validate that confidentially has been
maintained. According to Guba and Lincoln (1985), the member checking technique
allows research participants to check and confirm their answers for credibility and true
representation. After each interview, I gave 30 minutes to each participant to check all
their answers to make sure it is what they want to say. For participants who do not wish to
participate in member checking their transcripts will be accepted as final and used for
analyses. Wurie (2012) used member checking technique to enhance and strengthen data
credibility.
Issues of Trustworthiness
The credibility of qualitative data is equally important as it is in a quantitative
study (Shenton, 2004). For the data of qualitative research to be trustworthy, the
information obtained in the field should be credible, transferable, dependable, and
confirmable (Shenton, 2004). Credibility is the process of revealing what exactly
happened in the field (Shenton, 2004). To obtain credible data, a researcher should use the
triangulation strategy, member checking, peer debriefing, and observation (Shenton,
2004). Lincoln and Guba (1985) and Shenton (2004) explained triangulation as using
many sources of data collection to check inconsistencies. Apart from the interviews, I will
access data from the websites of U.S. DHS, Mexico Health Department, and U.S. BPC to
check insistencies for credible data. I used a colleague student at Walden who is interested
in the topic for peer debriefing. I posted the announcement on Walden students’

189
dissertation groups on Facebook for interested person. The person sent me a private
message on Facebook messenger accepting to debrief my findings. We are not acquainted.
The person signed a confidentiality agreement and focused mainly on checking my
personal biases and perceptions. The debriefing process started soon after interviews were
conducted and ended after data analysis. I emailed the interview notes or transcripts to the
person. I used the member checking technique and according to Shenton, member
checking allows participants to make corrections to reflect what they wanted to say to
make sure the information provided is true.
To achieve transferability which refers to where the findings of one study can be
used in different settings (Lincoln & Guba, 1985; Shenton, 2004), the researcher should
allow participants to provide detailed information about the topic to generalize findings
(Lincoln & Guba, 1985; Shenton, 2004). This is in line with my selected
phenomenological approach. To achieve dependability, which refers to findings being
consistent and can be replicated (Lincoln & Guba, 1985; Shenton, 2004) semistructured
interviews were used to allow participants provide detailed information about the topic.
Finally, the last requirement to ensure data trustworthiness according to Shenton (2004) is
confirmability. This is where the researcher should be neutral to prevent biases and
provide an audit trail of all for the research (Lincoln & Guba, 1985; Shenton, 2004). The
triangulation method also enhances the confirmability of a study (Lincoln & Guba, 1985;
Shenton, 2004) which I employed.

190
Summary
Chapter 3 presented information on the design of the research, role of the
researcher, selection of research participants, and instrumentation. The study’s design is
phenomenology. Convenient sampling is used to select research participants. Recruitment
of participants was done on social media. Interviews were conducted using phone and
other internet-based electronic tools. ATLAS.ti software is used for data coding and
analyses. This chapter additionally described my study’s ethical procedures and issues of
trustworthiness for recruitment, interviewing, coding, and analyses.
The Chapter 4 presents findings of my in-depth interviews, data analyses, and
evidence of trustworthiness of the data collected. The chapter also presents characteristics
and information about the research participants. In this chapter, the responses provided by
the research participants are categorized into themes for easy analysis and understanding.
Chapter 4: Research Findings
Introduction
The study’s purpose was to understand the role of healthcare quality in Mexico in
undocumented immigration to the United States. A phenomenological research approach
was used to explore lived experiences of the research participants. This chapter presents
information about the research participants, their experience with undocumented
immigration to the United States, and healthcare in both Mexico and United States. The
chapter also presents research findings and data analysis.

191
Setting
All the interviews were conducted via phone. In total, seven participants were
interviewed; five participants agreed to speak to me in English while two participants
opted to do the interview in Spanish through the interpreter. Each interview lasted about
45 minutes and additional 30 minutes for member checking was needed once individual
transcripts were transcribed, cleaned, and formatted for sharing with the interviewed
participant.
After I received IRB approval (0986362; 05-26-22), I recruited all the seven
participants using a social media platform. I posted my recruitment announcement
(Appendix A) on my personal page wall. The people who had interest to participate
responded to the posting through direct messaging to my user account name. I then
provided them criteria for recruitment and the informed consent. Each of the seven
recruited participants completed the research interview in its entirety. I made no changes
to the informed consent after IRB approval as I did not change participants’ recruitment
process, data collection methods, analysis, and data storage.
Demographics
All seven study participants lived in the Hidalgo County, Texas, United States.
All the participants are adults who experienced healthcare both in Mexico and United
States. All participants speak English and Spanish and used to have jobs in Mexico. Out
of seven participants only two people did their interview in Spanish. To ensure
confidentiality, I used pseudonyms for all participants interviewed.
John
At his interview time, John was living in Hidalgo County, Texas. He is in his mid

192
40s and currently a truck driver in the United States. He came to the United States from
Mexico. He was truck driver too in Mexico. He had health insurance in Mexico and
currently has health insurance in the United States. John sent me a message to take part in
the study after reading the recruitment posting I posted on my social media page
(Appendix A). During the interview phone call, he declined the interview be
audiorecorded and agreed the interview to be conducted in English. John was polite and
clear during the entire process.
Juan
At his interview time, Juan was living at Hidalgo County, Texas and working as
car mechanic. He is in his early 40s. He immigrated to United States from Mexico in his
early 30s at Tamaulipas closer to the southern border. Juan was a car mechanic in Mexico.
He was fully insured at the time of this study. Juan sent me message after he read my
recruitment posting I posted on my social media page. He turned down my request to
audio-record his interview. He requested the interview to be conducted in Spanish through
the interpreter. His interview was done in Spanish. Juan was nervous when he answered
the interview phone call, but he became calm and relaxed when I started building rapport
and asking questions about his favorite food and car for the first 5 minutes. He was
comfortable, articulate, and audible in Spanish language. His interview lasted about 45
minutes.
Maria
At her interview time, Maria was residing at Hidalgo County, Texas and working
as a nurse. Maria is in her late 40s. In Mexico she was living at Reynosa a city closer to
the Mexican-U.S. border. She came to the United States in her early 30s. She was a nurse

193
in Mexico. Maria who saw my recruitment post in Spanish on my social media page and
sent me a message expressing interest to participate. Before her phone interview started,
Maria explicitly stated he wants the interview to be conducted in Spanish and should not
be recorded. Maria was happy throughout the interview process and was straight forward
in her responses. She was clear. Her interview lasted about 50 minutes.
Rosa
At her interview time, Rosa was residing at the Hidalgo County, Texas. Rosa was a
teacher in Mexico before coming to the United States and she had health insurance. She is
in her early 40s and teaches in middle school in the United States. She immigrated from
Palau Coahuila. Rosa replied to my recruitment post on my social media page and sent me
message expressing her interest in the study. During the phone interview call, she agreed
that the interview should be conducted in English but should not be recorded. She was
clear and detailed in her responses to the interview questions and answer all the questions.
Her interview lasted for about 30 minutes.
Perez
He is in his mid 70s. At his interview time, Perez was living in Hidalgo County,
Texas. He was born in Mexico, but he immigrated to the United States in his early 40s.
He was a welder in Mexico for more than 40 years. He had health insurance in Mexico.
Perez was working as a welder when he arrived in the United States, but now he is retired.
Perez sent me a message after he read my recruitment post on my social media page.
Before the interview started during the interview phone call, Perez opted for English
interview, but turned down my request to record the call. He was so emotional and

194
provided examples for probing questions. He remained calm throughout the interview and
provided concise and clear responses. His interview lasted for about 50 minutes.
Kiara
She is in her late 50s. At her interview time, Kiara was living at Hidalgo County,
Texas and working as nurse. She moved to the United States from Mexico when her
husband had work related accident in Mexico. In Mexico, Kiara used to work in one
factory called Maquiladoras. She had health insurance in Mexico because of her job.
Kiara read my recruitment post (Appendix A) on Facebook and sent a direct message to
me on Facebook. When I called her for the interview, she indicated she wants the
interview to be conducted in English, but she declined the request to record the call. Kiara
was open, detailed, and audible in her responses. The interview with her lasted for about
30 minutes.
Juliana
She is in her mid 40s and at her interview time lives in Hidalgo County, Texas.
Juliana immigrated to the United States from Mexico when she was battling with a
chronic hepatitis B and had medical issues with her liver. Juliana was a working in a
restaurant as waitress. She had healthcare insurance in Mexico. In the United States,
Juliana is working as parole officer. She read my recruitment post on my social media
page and sent me a message to show interest as participant. During the phone interview,
she agreed to speak English and turned down my request to record the call. Throughout
the interview she was calm, happy, and clear. The interview call with Julian lasted for
about 45 minutes.

195
Data Collection
I collected data from seven research participants using the semistructured
interview protocol (see Appendix B) to explore lived experience of the participants. All
the interviews were conducted via phone. Each interview lasted between 30 to 60 minutes.
I scheduled each interview at the convenience and request of each participant. I used 2
weeks to complete the interviews and member checking. Two of the interviews were
conducted in Spanish with professional interpreter and five interviews were conducted in
English. The settings for this were inside my room in Fort Worth, Texas and Hidalgo
County, Texas, for each respondent. All the interview calls initiated well and ended
successfully without any network interference or physical interruptions.
I asked each participant all questions on the interview document (see Appendix B)
and sometimes asked follow-up questions to clarify information or for in-depth
information during interviewing. All the participants separately turned down my request to
audio record the interview calls for privacy reasons. I spent about 40 minutes asking
interview questions and taking interview notes on each call. After the interview, I read the
responses provided to each respondent to confirm or modify their answers to reflect what
they really wanted to say. This member checking process was completed within 30
minutes for each participant. All the participants did the member checking for credible and
accurate data. I also used peer debriefing technique to check my own bias in data coding
and analysis. I converted the interview notes into a MS Word document for each
participant. I stored the data on electronic files in Dropbox (cloud) with backup on an
encrypted flash drive, which I stored in a locked cabinet. Some information about the

196
causes of undocumented immigration from Mexico to the United States was obtained
from the website of DHS. However, I could not assess or obtain information on the
challenges of healthcare accessibility in Mexico on the website of Mexico Health
Department. This was the only variation in the data collection plan outlined in Chapter 3.
Data Analysis
I used ATLAS.ti software to code and analyze the data. After I completed
interviews and member checking to confirm participants’ responses and make corrections,
I converted the interview notes of each participant into MS Word document. I applied the
iterative process (Pietkiewicz & Smith, 2014), which required that I and thoroughly and
closely read and reread the transcript, highlighting experiences of the participants on
challenges of healthcare in Mexico to influence to immigrate to the United States for
healthcare access. As I listened to participants and asked follow-up questions during the
interviews in addition to reading the interview notes I found some statements and words
that helped me to understand the experiences of the participants about the role of
healthcare in Mexico in undocumented immigration to the United States.
Using the ATLAS.ti software, I uploaded each participant’s responses and the DHS
website’s article on undocumented immigration in a form of word document and assigned
codes to the statements related to the research question. For the first cycle coding, I used
descriptive coding method. Here I described each participant’s response with simply
words and statements. For the second cycle coding, I used concept coding where I
assigned concepts to the descriptive statements in the first cycle coding. Finally, I looked
for patterns and similar concepts in participants responses I and grouped those patterns
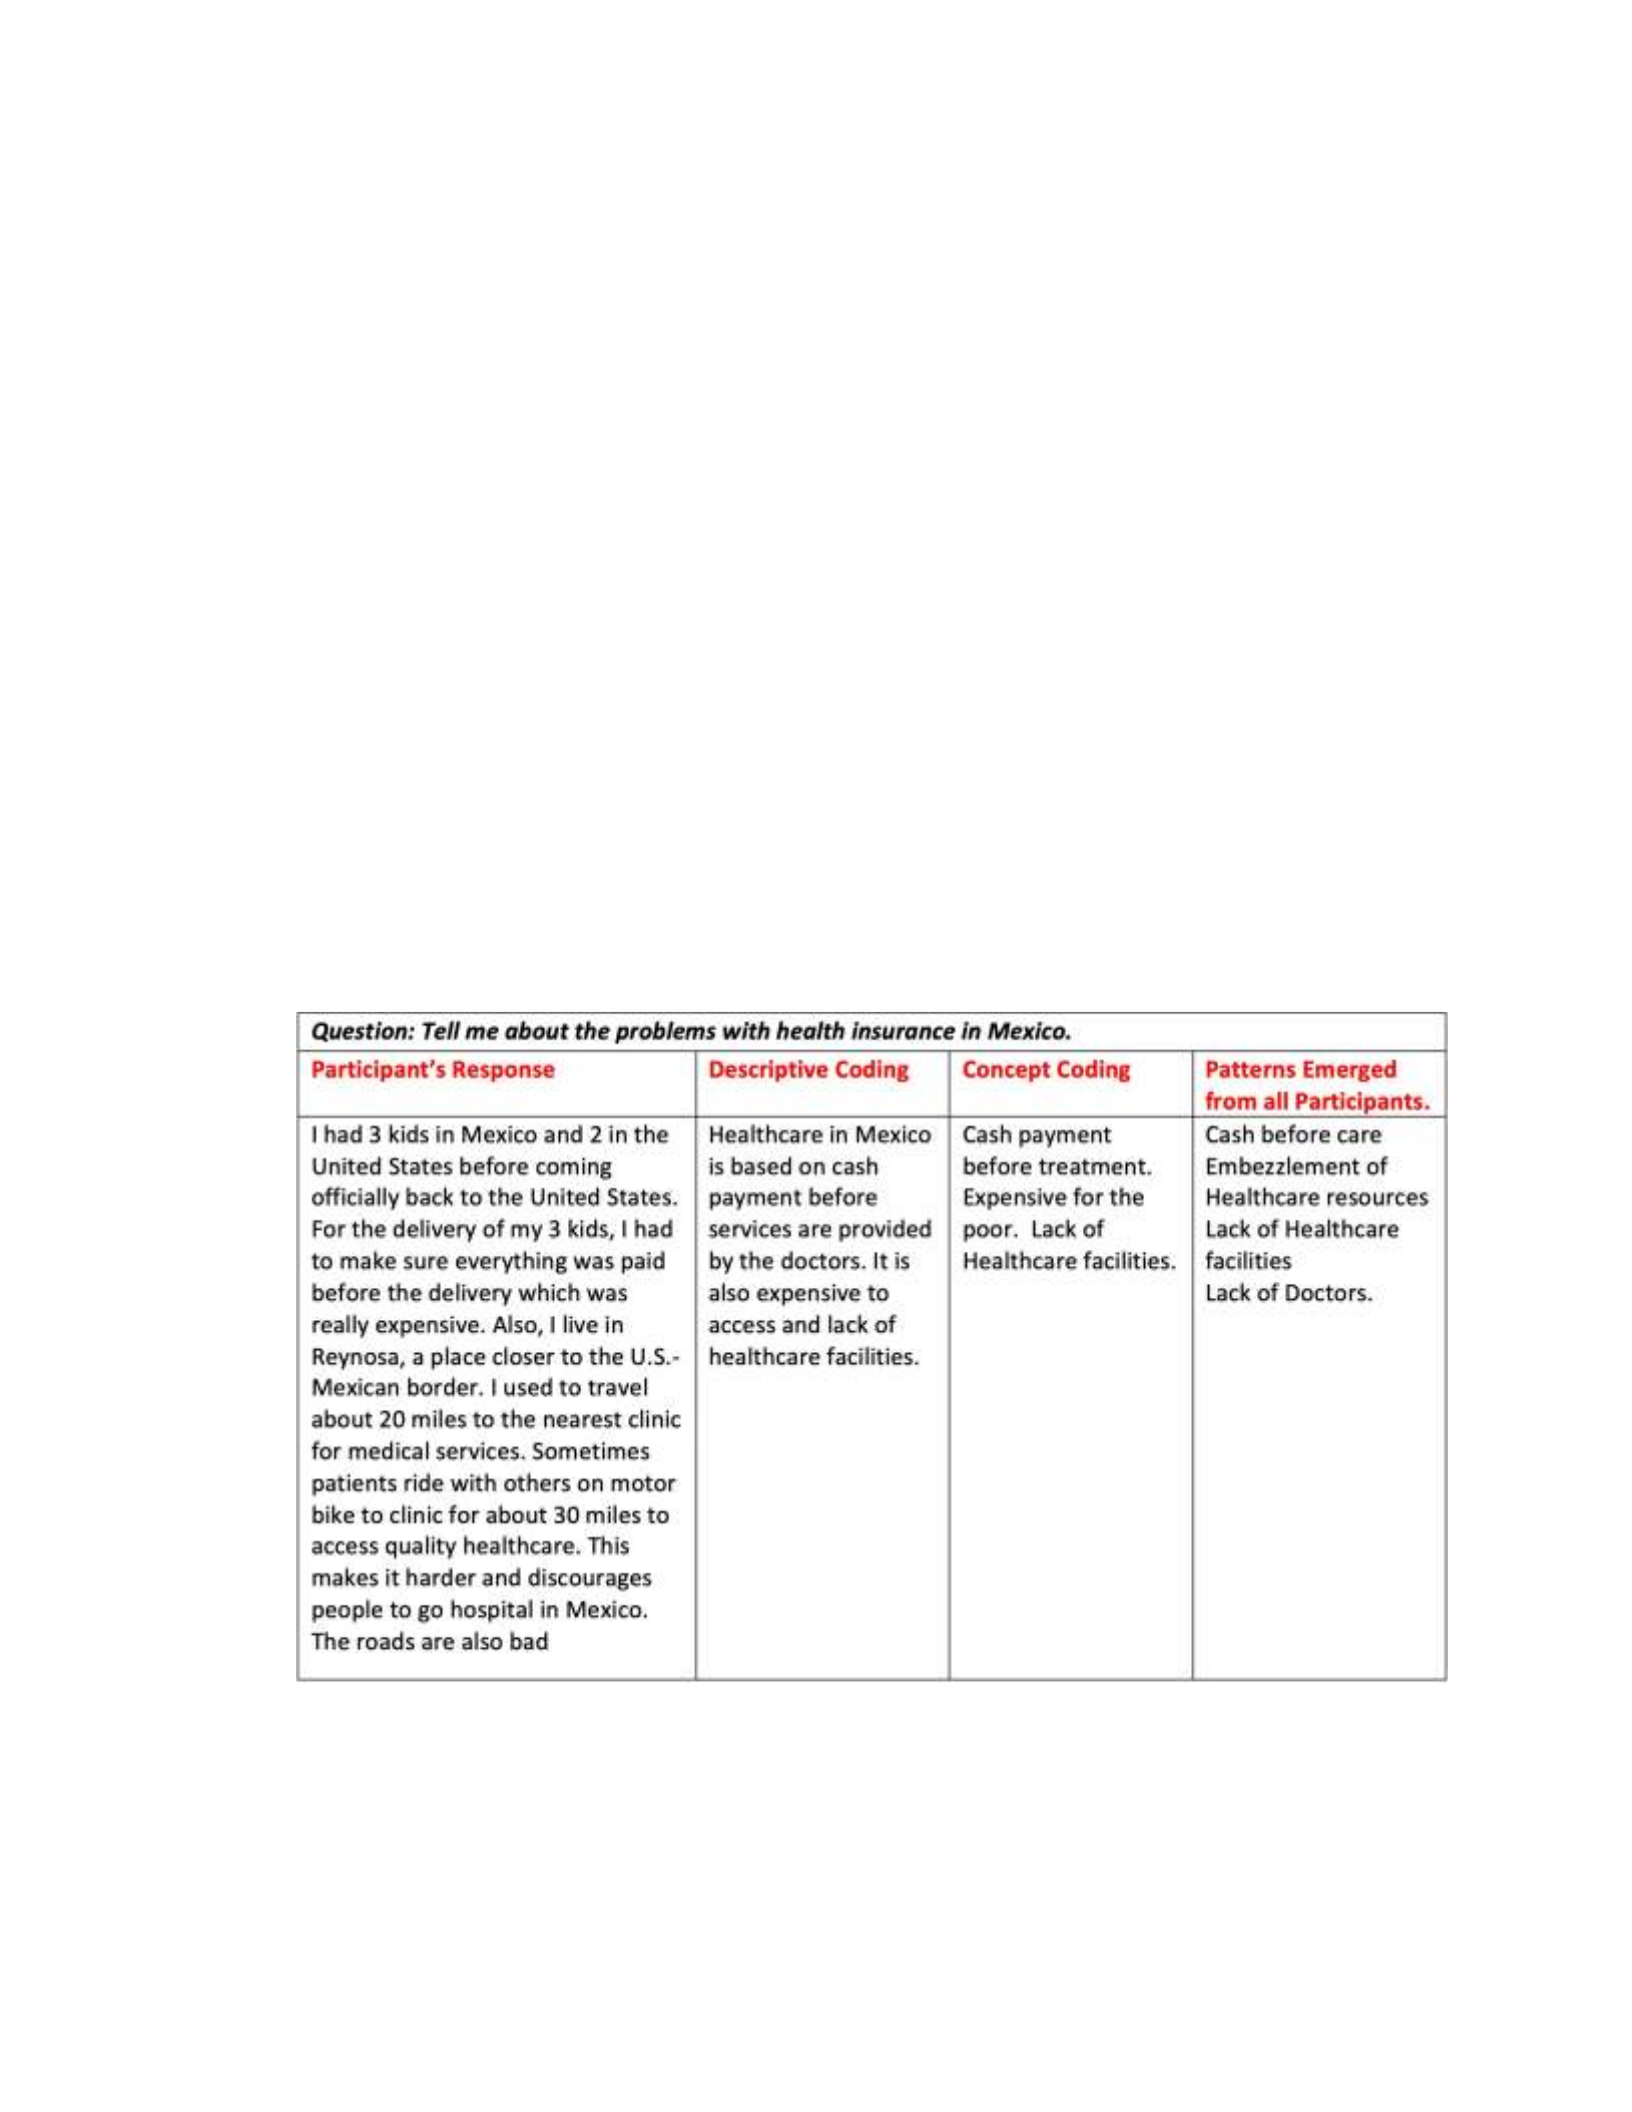
197
into themes. The Figure 3 below illustrated and summarized the coding process I used.
Some of the themes I generated relating to challenges of healthcare in Mexico (push
factors) included: (a) paying cash before receiving medical services, (b) corruption, (c)
lack of hospitals or clinics at the rural areas, and (d) lack of personnel or doctors.
Themes I generated on the pull factors of health insurance in the United States included:
(a) cheaper price, (b) perception of free medical services in emergencies, and (c) quality
healthcare services.
Figure 3
Coding Process
Note. The figure is an output of ATLAS.ti used in the coding. It illustrates the processes
followed. This process was repeated for each participant’s responses to generate the
themes.

198
I noted discrepant views or cases in the data coding and analysis. Patton (2015)
explained that data discrepancy strengthens and shows the in-depth nature of data
patterns. I used the discrepant data to understand and validate different reasons people
have to immigrate to the United States. I compared the discrepant data to the main data
and realized that the discrepant data described availability of jobs as the primary driver of
immigration to the United States. This reason opens the gate for more research to
appreciate and understand the overall picture of immigration.
Evidence of Trustworthiness
To achieve data credibility, I followed the plan I outlined in Chapter 3. To ensure
the data represent the actual view of the research participants, I used a member checking
technique to make sure I read each participant’s answers to them. This process provided
an opportunity for me to make corrections for the data to be credible and reflect what the
participants really wanted to say. I also used triangulation method by comparing data from
the interviews to information obtained from the website of DHS about reasons Mexicans
immigrate to the United States. I also thoroughly compared data of each participant to
ensure consistency and accuracy.
To achieve data transferability, I employed phenomenological research approach
and semistructured interviews. This method allowed the participants to provide in-depth
information and thick descriptions of their experience about the role of health care in
Mexico in undocumented immigration to the United States. According to Shenton (2004)
and Patton (2015) phenomenological study and semistructured interviews allow the
researcher to obtain detailed information to achieve data replicability and generalizability.

199
I also used a convenient purposive sampling strategy to select participants who have more
information about the topic. This helped me to achieve data transferability and
applicability of the findings.
I followed the plan explained in Chapter 3 to ensure data dependability. To ensure
consistency and reliability of my research findings I consulted my committee chair and
committee member when developing the interview questions to make sure all the
questions are realistic, aligned with the research question, and consistent with each other
(see Appendix B). Finally, because I used semistructured interviews, I was able to ask the
participants follow up questions for clarity and more information to make sure my
findings are dependable and consistent.
To achieve data confirmability, I used peer debriefing technique. As I explained in
Chapter 3, I posted the announcement on Walden students’ dissertation groups on
Facebook for interested person. The person sent me a private message on Facebook
messenger accepting to debrief my findings. The process started when I completed
interviews and ended when I finished data analysis. The peer reviewer double checked
interview notes, codes, and interpretations to make sure they are free from my personal
bias. Moon et al. (2016) explained that for data to be considered reliable, the researcher
must provide a detailed description of the methods, procedures, and processes used in
drawing conclusions for potential replication by others. All these procedures are explained
in Chapter 3. I also used member checking technique and research reflexibility on my
personal beliefs and perception to be neutral and transparent in data collection and
analysis to maximize confirmability.

200
Results
My research question was: What are the lived experiences of formerly
undocumented Mexican immigrants living in Hidalgo County, Texas, regarding the role of
healthcare in their decision to migrate to the United States? I used semistructured
interviews to explore lived experiences of the research participants. The data were
organized in MS Word document. I used ATLAS.ti software, descriptive and concept
coding strategy to code the research data. The themes that merged relevant to the push
factors included: (a) paying cash before receiving medical services, (b) corruption, (c)
lack of healthcare facilities at the rural areas, and (d) lack of doctors. These problems as
push factors, forced some participants to leave Mexico. The other themes that were
generated relating to the pull factors of healthcare insurance in the United States are: (a)
cheaper health insurance for healthcare, (b) perceived free medical services in
emergencies, and (c) quality healthcare services. The pull factor themes motivated and
encouraged some of the participants to migrate to the United States to access quality
healthcare. The study’s push/pull factor themes and discrepant data are discussed in this
section.
Theme 1: Pay Cash before Receiving Medical Services
The study’s findings revealed that the role of healthcare in Mexico in
undocumented immigration to the United States is, that people in Mexico more at times
are required to pay upfront for medical services even though they are insured. Based on
the comments by the respondents to pay cash before seen by a physician limited access to
quality healthcare especially the poor. Five of the seven respondents shared their views.

201
For instance, Juan noted “in order to have health insurance in Mexico you need a job.
Health insurance in Mexico is all about money and no doctor will you see you without
money even when you have insurance.” He added, that in Mexico to have any medical
procedure done you need to have the money right there and then. You cannot have any
medical procedure done without the money.
Maria stated “I had 3 kids in Mexico and 2 in the United States before coming to
the United States. For the delivery of my 3 kids, I had to make sure everything was paid
before the delivery which was really expensive.” According to Perez, it is hard to obtain
health insurance in Mexico, even if you have insurance everything is expensive. Rosa
summarized her experience in Mexico about paying cash before a doctor attend to you.
She stated “sometimes my doctor would ask me to buy injections from pharmacy and
bring them to the hospital for injection or treatment. It was appalling and disgraceful.”
Finally, commenting on the challenges of health insurance in Mexico, Kiara explained that
“in Mexico my insurance really didn’t cover anything, I had to pay everything upfront
even for the deliveries of my babies. I was always scared of needing emergency insurance
due to the money.” She expressed her view that physicians or nurses in Mexico have
prioritized money over human life and welfare.
Theme 2: Corruption and Embezzlement of Public Funds or Resources
All the 7 participants described how corruption and embezzlement of public
resources made it difficult for healthcare access in Mexico. John felt that many people in
Mexico have no access to healthcare because some politicians and public administrators
used public funds meant for expanding healthcare access for personal gains. He stated

202
“politicians and administrators in Mexico are corrupt to the core. The empty public coffers
for personal gains to the detriment of the poor to access quality healthcare.” Juan asserted
that corruption is the root cause of ineffective health insurance system. He narrated “my
friend used to tell me how some administrators in the Health Ministry in Mexico always
channel public funds meant to help the vulnerable to access healthcare for personal
benefits.” He described the situation as a “curse.” Maria who shared similar view with
Juan on corruption further explained that “everything is already planned out about making
it difficult for the poor to always suffer and the rich corrupt politicians continue to be
rich.” She felt the situation is unfair and disgusting.
Perez was emotional in describing the impact of corruption on healthcare access.
He stated “in Mexico corruption is bad, I don’t like talking about it; it’s politics. I try to
not get involved in them.” Even though he was not interested in talking about corruption,
he described it as a “sin” against the public and vulnerable as it denied them basic right to
have access to quality health care. Expressing her experience Rosa explained that
corruption is the main challenge for the people to access health insurance as corruption
leads to inadequate funds to expand access to healthcare. Kiara noted “public
administrators in charge of managing public funds for public good are rather using the
funds to buy nice houses and luxury cars draining the coffers meant to help expand health
care to the people at the rural areas and pay physicians.” Juliana had a moment to reflect
on her experience on corruption as a problem of health insurance in Mexico. She said her
father one narrated to her how politicians in Mexico have been using state resources for
personal gains. She lamented “One of the biggest problems of insurance in Mexico is

203
corruption.” She defined corruption as a situation where a public official uses public
resources such a money to satisfy his/her parochial interest while the vulnerable continue
to suffer.
Theme 3: Lack of Healthcare Facilities at Rural Areas
Four out of seven participants mentioned lack of healthcare facilities in rural areas
as one of the challenges of healthcare access in Mexico. Maria stated “I live in Reynosa, a
place closer to the U.S.-Mexican border. I used to travel about 20 miles to the nearest
clinic for medical services. Sometimes patients ride with others on motor bike to clinic for
about 30 miles to access quality healthcare. This makes it harder and discourages people
to go hospital in Mexico.” She added that some roads to certain clinics are nonmotorable.
According to Perez, inadequate number of health facilities leads traveling long
distances to access healthcare discourages some people to go to hospitals to seek
treatment. He stated, “healthcare facilities are congested in urban areas or cities, but many
rural areas lack clinics and hospitals and even roads leading to the few healthcare facilities
in the rural areas are deplorable.” He explained further that nurses and physicians do not
want to station at rural areas to provide quality healthcare to people who need as every
nurse and physician want to work in cities. These challenges increase waiting time to see a
nurse or doctor. Perez narrated that 50 years ago he visited a clinic in and waited a long 3
hours in a line to see a nurse. Finally, he and other 3 patients had to go back home without
seeing any nurse or attended to.
At Tamaulipas, closer to the Mexican-U.S. border, Juan explained that
unavailability of healthcare facilities such as clinics and hospitals denied some people to

204
access healthcare. He said he used to traveled long distance for about 3 hours on motor
bike to the nearest hospital to seek treatment. Juan posed an important question in
explaining his answer. He stated, “imagine what happens to patients who lived in my area
but who do not have motor bikes or cars to travel to the nearest hospital?”. Finally, in
addressing the question concerning challenges of healthcare access in Mexico, Juliana
explained that she used to travel about 6 miles on foot to the nearest hospital to access
healthcare. She stated “I went through hell” because of inadequate number of hospitals
and clinics in Mexico and lack of means or transportation to go to the clinic or hospitals.
Theme 4: Lack of Doctors
In explaining challenges of healthcare access, three out of seven participants
narrated their experience about lack or shortage of healthcare personnel affected their
access to healthcare in Mexico. In accounting her experience, Kiara stated “not having
enough doctors and nurses at hospitals and clinics is another problem making it harder on
people to access healthcare in Mexico. This results in long hours to see physicians and
nurses when you visit a facility. I remember on about three instances I had to wait in line
for more than 2 hours to see a doctor. It was terrible.”
Juliana explained that healthcare access is essential but lack of nurses and
physicians in Mexico has denied many people to access quality healthcare. She stated that
during the time she was diagnosed with hepatitis B she would go to a public hospital for
checkup and the doctor would not show up or she could wait for about 3 hours, because
the doctor had private hospital to attend to patients in that hospital. According to Juliana it

205
is because of lack of doctors in public healthcare facilities that made her experienced what
she explained, and it is a challenge for accessing quality healthcare in Mexico.
Finally, Rosa also shared her experience about lack of doctors in public hospitals
as a problem of healthcare access in Mexico. She narrated “before I immigrated to the
United States, there was doctor in my community’s government hospital in Mexico. The
hospital only had nurses who are not trained to do surgeries and other complicated
medical conditions.” She explained further that lack of specialists in hospitals discourages
people to visit hospitals when they are sick and that complicates medical conditions
needing more attention and money for treatment.
The themes that were generated as pull factors of immigration to the United States
from Mexico for healthcare access are discussed below: it was a probing question put
before all participants.
Theme 1: Perceived Free Access to Healthcare in Emergencies
During the interviewing four out of seven participants explained their experience
as undocumented immigrants about free access to healthcare in emergencies is a pull
factor for immigration to the United States from Mexico. Kiara accounted that: I knew
as an undocumented I could go by the hospital anytime and I would be given healthcare
access without insurance if my medical condition is critical. And
I would not pay anything to see a doctor in emergency which is not possible in
Mexico.
She added “If I’m honest I feel safer in the United States than Mexico.” She also added:
My husband had a lot of health problems and while living in Mexico we couldn’t

206
afford anything. We decided to move to the United States because of him, he had
more access to healthcare here through the help of some organizations. He passed
away about 3 years ago due to a work accident, he wasn’t denied healthcare access
due to no insurance. He was even transported via a helicopter to another city end
up to this date we have not been charged a single dime for it.
Maria also said
When I came to the United States before I become legal permanent resident, I had
2 surgeries as emergency and did not pay nothing. I also had my two daughters
here; I wasn’t expected to pay anything for them as well. On the contrary I was
given health insurance and for my baby while I was pregnant. Both of my kids had
access to free Health insurance which was a great benefit. In the United States the
healthcare services are more quality than services in Mexico. They have better
medicines and doctors and equipment.
Rosa also explained that when she arrived in the United States from Mexico:
I was able to see that in the United States health insurance access was way easier. I
did not have health insurance here yet due to being illegal, but I went the hospital
anytime and I would be given healthcare access without insurance in life
threatening situations. And I would not pay anything to see a doctor under
emergency which is not possible in Mexico.
Finally, during the interview process Juan also shared “I moved to the USA because of job
and healthcare access. Health insurance in the United States is more accessible. If I need
to go to the hospital, I don’t have to worry about having to pay before being seeing a

207
doctor. I was admitted to emergency room when I had car accident. I did not pay any
money before I was attended to. There is quality healthcare.”
Theme 2: Cheaper Health Insurance for Healthcare
Three of the participants explained that undocumented immigrants in the United
States buy health insurance at cheaper rates compared to documented immigrants and
citizens. According to Maria, it is not expensive for undocumented to buy health insurance
as some non-profit organizations help undocumented to acquire insurance. She noted
“many healthcare centers here funded by the federal government offered health insurance
at cheaper rates to the poor including the undocumented immigrants. After my surgeries as
an undocumented I bought health insurance at rate of $40 a month at Hidalgo Health
Center which is more expensive for documented immigrants and citizens who work.”
Juan narrated that accessing healthcare is cheaper for undocumented immigrants in
the United. She stated “there are independent charity organizations like Kaiser
Permanente Bridge Program which made me to apply for low-cost medical services. You
don’t need a social security number to apply. I applied and was approved. I paid $35 a
month just for primary healthcare services”. The enrollment helped me a lot to access
healthcare at lower prices when I was undocumented.
Finally, in the interview Rosa shared her experience that as an undocumented,
accessing health care insurance is cheaper and easier for her. She explained that some
health facilities and hospitals receiving some federal funding provide health insurance at
cheaper rate to poor person including undocumented immigrants who cannot afford to pay
for higher rates. She continued “for instance when I arrived in the country as

208
undocumented the Catholic Church, I attend, provided me the necessary financial help to
acquire health insurance and later I bought insurance at cheaper rate of $40 a month until I
become documented.” Healthcare services were also provided by newly trained doctors at
San Antonino hospital at lower cost or free to poor people and undocumented immigrants
according to Rosa.
Theme 3: Quality Healthcare Services
All seven participants agreed and stated that there are better quality healthcare
services in the United States than in Mexico. However, four out of seven participants
admitted that the availability of the quality healthcare services in the United States
influenced their decisions to relocate to the United States. Maria is noted to have explain
that there are better doctors, machines and medicines in the United States compared to
Mexico and everyone is interested in accessing what is better. She added that she had two
surgeries as an undocumented immigrant in the United States and had seen better
equipment, doctors, and medicines in the whole process. According to her Mexican
hospitals and healthcare facilities lack some of these equipment, specialized doctors, and
medicines.
Kiara also indicated that quality of healthcare services is better in the United
Sates than Mexico because of the technology gap between Mexico and United States.
Rosa also mentioned that she migrated to the United States because she believed there are
better doctors and medicines in the United States and that is proven when she visited
hospital for the first time as undocumented immigrant. She said, “the doctors were nice
and kind to me and would speak soft words to me and give me hope all the time but in

209
Mexico sometimes doctors would be treating me like trash and don’t care about I feel”.
Finally, Juan also mentioned that she moved to the United States because of healthcare
access. She explained that United States has more sophisticated and modern medical
machines and tools and more specialized doctors than Mexico. She narrated “I feel safer
and confident in the quality of healthcare I received in the U.S. than in Mexico even
though sometimes it is more costly than Mexico. However, in all U.S. is better than
Mexico in terms of quality of healthcare access. Figure 4 below summarized themes of
the research findings by illustrating reasons some of the participants migrated from
Mexico to the United States.
Figure 4
Push/Pull Factors of Migration
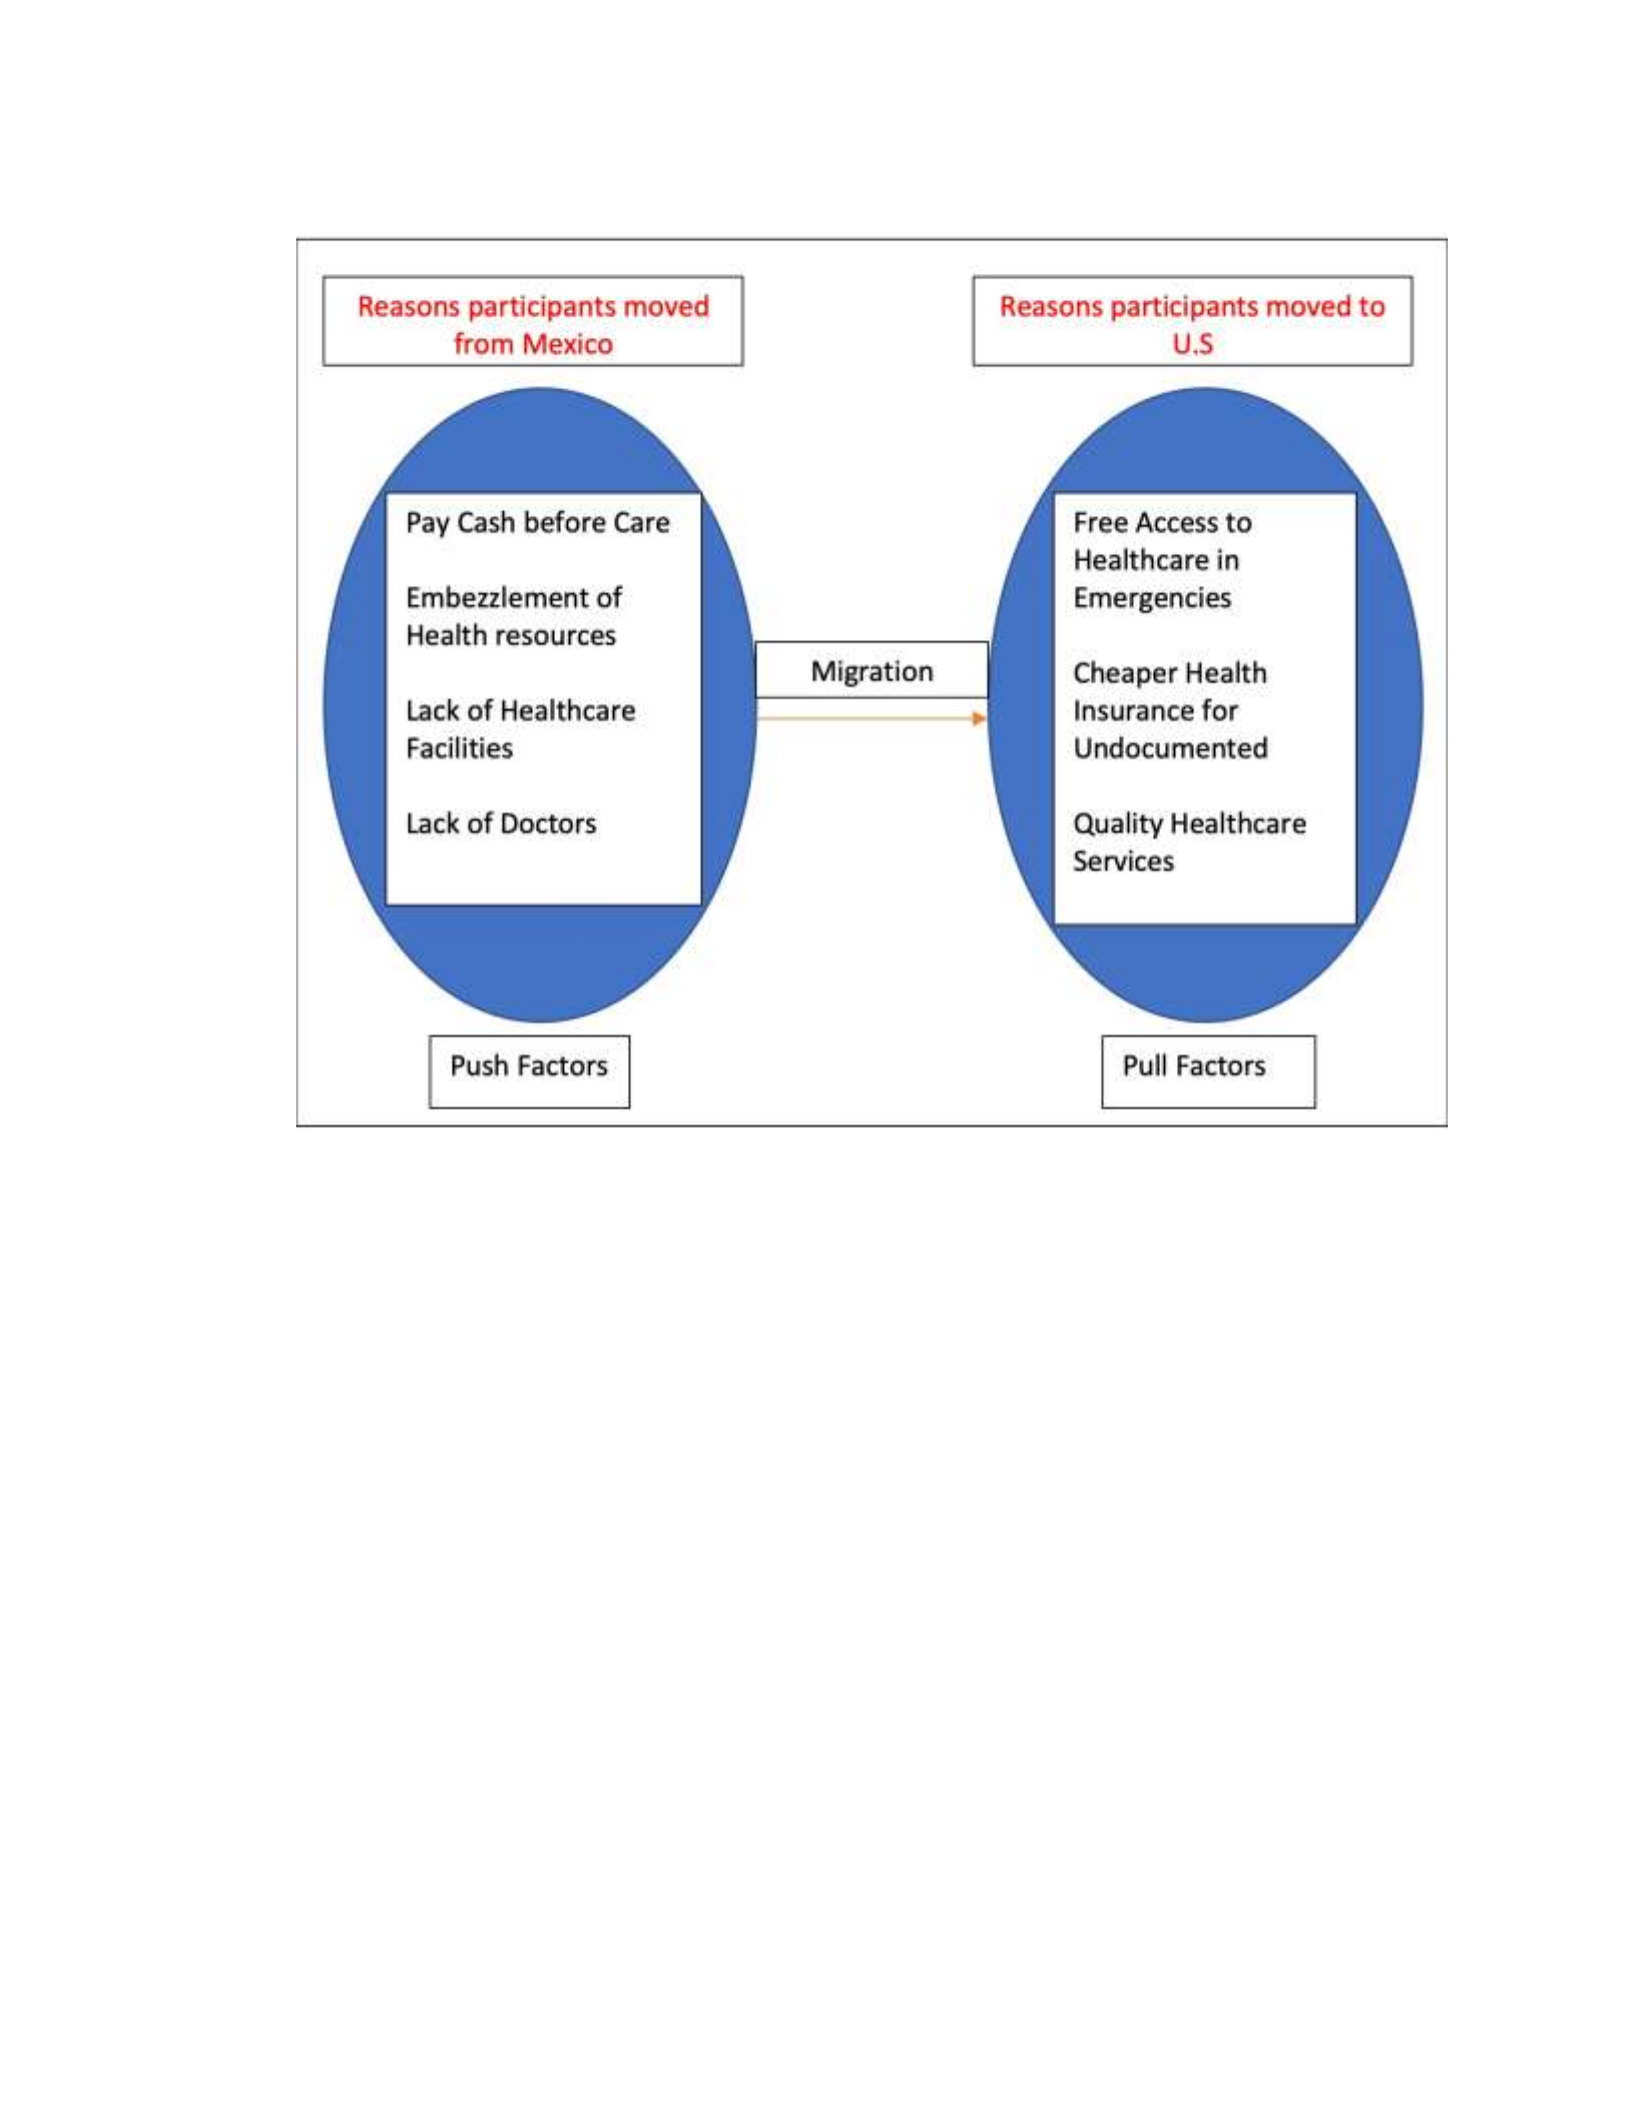
210
Note. The figure illustrates reasons some of the participants migrated from Mexico (push
factors) and reasons they migrated to the United States (pull factors) for healthcare access.
Discrepant Data
Discrepant data is normal in research studies and proves quality of data (Miles et
al. (2014). During the interviews, three out of seven participants explained that they
moved to the United States because of jobs opportunities and reuniting with families, but
not because of healthcare access. According to Perez “I immigrated to the United States
because of my family”. Also, John in answering one of the follow-up questions about why
he migrated to the United States said the decision to migrate was family decision and they
moved here because of jobs availability. He answered “No, I would not but healthcare

211
insurance is better here. We came here because of availability of jobs.” Finally, Juliana
also stated that she migrated to the United States to find better job, earn good income to
take care of the family. According to the U.S. DHS (n.d.) the primary driver of
immigration to the United States is the availability of jobs opportunities and family
reunion.
Summary
The main research question is, what are the lived experiences of formerly
undocumented Mexican immigrants living in Hidalgo County, Texas, regarding the role of
healthcare in their decision to migrate to the United States? The main purpose of the
research question is for me to explore the lived experiences of participants about the
problems of healthcare access in Mexico motivating them to immigrate to the United
States to access quality healthcare. To explore those experiences, I composed a
semistructured interview script, conducted interviews, and analyzed the data to discover
emerging themes.
In responding to the question about problems with health insurance in Mexico,
participants mentioned embezzlement of public health resources for personal gains, lack
of healthcare facilities at the rural areas, lack of doctors, and pay before care as major
challenges. And in responding to the question about the healthcare benefits in the United
State which could serve as pull factors, the participants mentioned the perception of free
healthcare access in emergencies, cheaper health insurance for undocumented immigrants,
and quality healthcare services. He explained why people moved from an area or location
to different place. The results from the analysis explained healthcare reasons some of the

212
participants migrated from Mexico to United States. However, the primary leading factors
for immigration to the United States are availability of jobs in the
United States and reuniting with families.
Chapter 5: Discussion, Conclusions, and Recommendation
Introduction
The study’s purpose was to understand the role of healthcare quality in Mexico in
undocumented immigration to the United States. I used a phenomenological approach to
explore detailed and in-depth information from the research participants on how
challenges or problems of health insurance in Mexico could encourage some Mexicans to
cross to the United States to benefit from a free or lower cost of health care. My
conceptual framework is situated on Lee’s push/pull theory. The study’s focus was to
collect data from formerly undocumented immigrant from Mexico to understand
healthcare access challenges in Mexico that motivated them to enter United States as
undocumented immigrants.
The study’s key findings about challenges of healthcare access in Mexico include
embezzlement public health resources, payment before treatment, lack of healthcare
facilities at the rural areas, and lack of doctors in public hospitals. The key findings about
healthcare reasons which motivated some participants to migrated include a perception of
free access to healthcare in emergencies, cheaper health insurance for undocumented
compared to documented due to charity and other U.S. government funded programs, and
quality healthcare services. The key findings align with Lee’s push/pull theoretical
framework.

213
Interpretation of the Findings
The main research question is what are the lived experiences of formerly
undocumented Mexican immigrants living in Hidalgo County, Texas, regarding the role of
healthcare in their decision to migrate to the United States? I used two main interview
questions to explore the research question. One main interview question was focused to
explore problems of healthcare access in Mexico. The other question centered on the
benefits of healthcare in the United States that motivate undocumented immigrants to
immigrate to the United States from Mexico. Interpretations of the findings for these
questions and the literature reviewed in Chapter 2 are discussed below.
First, most of the research participants (5 of 7) stated that payment in cash before
receiving medical services is a challenge to healthcare access in Mexico especially among
the poor. The literature reviewed in Chapter 2 about healthcare access in Mexico
confirmed this finding. Martinez-Martinez and Rodriguez-Brito (2020) stated that Mexico
has one of the highest out-of-pocket healthcare expenses among the countries belonging to
the Organization for Economic Co-operation and Development and some doctors
requiring patients to make payments before being attended to. This makes it harder for the
poor and vulnerable to access healthcare in Mexico. To support this Pelcastre-Villauerte et
al. (2017), mentioned that in Mexico, 73% of the population live below poverty and face
challenges to get insured or pay their medical bills. Also, all the participants have
identified corruption and embezzlement of public resources as another problem for
providing quality healthcare for people in Mexico. This is confirmed in the literature
reviewed as Hone and Gómez-Dantés (2019), Rivera-Hernández et al. (2019), and Sosa

214
and Sosa-Rubi (2016) contended that presence of corruption and mismanagement of
public resources in Mexico is a key challenge to provide and expand healthcare access to
the people.
Additionally, the findings revealed that lack of healthcare facilities in rural areas in
Mexico makes it difficult for the people living in these areas to access quality healthcare.
Most of the participants shared their long travel experiences to find hospital or clinic. The
lack of healthcare facilities in rural areas is confirmed by the literature reviewed.
According to Hone and Gómez-Dantés (2019), Rivera-Hernández et al. (2019), and Sosa
and Sosa-Rubi (2016) lack of healthcare facilities in the rural areas has denied many
people especially in rural areas to accessible quality healthcare in Mexico. Finally, on the
problems of healthcare access in Mexico, majority of the research respondents identified
lack of doctors in the public hospitals. Each of those participants explained how lack of
doctors affected them in Mexico. As reviewed in Chapter 2, Hone and Gómez-Dantés,
Rivera-Hernández et al., and Sosa and Sosa-Rubi collaborated on lack of healthcare
personnel and doctors as a challenge to addressing inequities of healthcare access in
Mexico.
To begin with, my study’s findings revealed that majority of the research
participants immigrated to the United States because they had a perception that they are
entitle to free healthcare services in emergencies, despite this fact being untrue for the
providers of those healthcare services. According to my findings, participants had
information and beliefs that during emergency situations doctors in U.S. hospitals and

215
clinics are required by the federal law to treat patients regardless of their background or
immigration status. This finding coincided with the literature reviewed. Kuruvilla and
Raghavan (2014) clearly stated that hospitals that receive federal funding in the United
States must screen and stabilize patients who need emergency care for free regardless of
their immigration status and ability to pay. Emergency care is backed by EMTALA, which
was first signed into law in 1986. Castaneda (2016) stated that in many large medical
schools, medical students provide free health care to the poor including undocumented
immigrants as part of their training rotations. However, according to Sawyer (2017), the
perceived “free” care is never free to the provider. American College of Emergency
Physicians (n.d.) added that emergency physicians on average provide $138,300 of
EMTALA charity care each year and incur on average $25,000 EMTALArelated-bad debt
in 2001 per the research conducted by American Medical Association (AMA) in May
2003. Further, the American Hospital Association (2021, February 28) has estimated that
approximately $660 billion dollars in the past 20 years has been spent in EMTALA and
other unfunded care resulting in upwards shifts of pricing to cover costs directly
impacting consumers and business alike.
The findings also revealed that healthcare insurance is cheaper for undocumented
immigrants in the United States. Some of respondents shared their experiences of
acquiring lower-cost health insurance from some community healthcare services and
nonprofit organizations. This information is confirmed by the literature in Chapter 2.
According to the literature some community health facilities, churches, and non-profit
organizations help undocumented immigrants to get health insurance at lower cost

216
(Artiga & Diaz, 2019; Castaneda, 2016; Flavin et al., 2018; Kuruvilla & Raghavan, 2014).
Also as already stated, in some larger medical schools’ medical students provide free
medical services to the vulnerable including undocumented immigrants (Castaneda,
2016).
Finally, some of the participants also mentioned that the healthcare services in the
United States are of higher quality than services provided in Mexico. They explained that
United States has better medical equipment and specialized doctors than Mexico. And this
has influenced their decision to move to the United States. This finding is not confirmed
by the literature reviewed.
By and large, these findings are aligned with the conceptual framework for this
study (Lee’s push/pull theory). Lee articulated that migration is caused by both push and
pull factors with intervening obstacles (Lee, 1966). The push factors according to the
findings are the challenges for healthcare access in Mexico. They are: (a) payments are
made before treatment, (b) corruption or embezzlement of public resources for personal
gains, (c) lack of healthcare facilities, and (d) lack of personnel or doctors in public
hospitals. The pull factors according to the findings are conditions in the United States
that promote access to quality healthcare to undocumented immigrants. They are: (a)
perceptions of free access to healthcare in emergencies, (b) cheaper health insurance for
undocumented immigrants, and (c) more quality healthcare services. The intervening
obstacles included hunger and fear of being shot or arrested.

217
Limitations of the Study
One of the study limitations is that majority of the interviews were not audio
recorded. This might have affected the quality of data collected, due to the difficulty
presented by listening to participants and taking notes simultaneously during interviews
(Ravitch & Carl, 2016; Rubin & Rubin, 2012). Secondly, I used a nonprobability
sampling technique to select the research participants. This technique, according to
Ravitch and Carl (2016), lacks randomness and enhances potential researcher. However,
Moustakas (1994) argued that the nonprobability technique can be used in qualitative
research because qualitative research focuses on discovering and providing in-depth
information on a topic to provide a better understanding but not how often something
happens. In addressing this, I used a nonprobability, convenient purposive sampling to
explore detailed and in-depth data. I also used triangulation, peer debriefing, and
bracketing strategies to check my personal bias to strengthen the credibility and
trustworthiness of the research findings. Finally, I used member checking technique to
double check and confirm answers participants provided to ensure the answers captured
were the correct answers participants wanted to provide to achieve data credibility.
Recommendations
There are two recommendations that emerged. The study was only conducted in
Hidalgo County, Texas. The study can be replicated in other neighboring counties and
states to study the overall impact healthcare benefits have on undocumented immigration
to the United States. According to the literature reviewed in Chapter 2, California is the
first state in the United States to provide state government-subsidized health benefits to

218
young undocumented immigrants (Allyn, 2019). This is an avenue for future research.
Another possible research area in the future is to widen scope of the study to include other
countries such as El Salvador, Cuba, East Africa, and West Africa as number of
immigrants in those areas keep increasing (Justice for Migrants, 2017 & Murtaza, 2020).
Implications
Finding ways to identify challenges for healthcare access in Mexico, the findings
will enlighten people about the role of healthcare in Mexico as a push for undocumented
immigration to the United Sates. The findings will also have positive implications for
social change in the field of public policy since it will add to our understanding of the
relationship between healthcare and immigration. It will also provide useful information
to the Hidalgo County local health department officials and United States Immigration
policy setters to better guide their debate and policies on healthcare policy. Also, the U.S.
Government needs to spend more time and resources to disabuse persons of the
information that emergency healthcare is “free”. The findings also revealed that the
primary factors leading of immigration to the United States are jobs availability and
reuniting with families and this information should help guide policies and debate on
immigration.
Conclusion
The study’s purpose was designed to understand the role of healthcare quality in
Mexico in undocumented immigration to the United States. The main research focused on
exploring the lived experiences of formerly undocumented Mexican immigrants living in
Hidalgo County, Texas, United States. A phenomenological approach was used. A

219
convenient non-probability sampling techniques was used to select all the research
participants. The conceptual framework was Lee’s push/pull theory of migration.
Based on the findings, majority of the research participants stated they moved to
the United States as undocumented immigrants to access quality healthcare. The research
findings are in line with Lee’s push factors of migration as the healthcare challenges in
Mexico served as the push factors. There are (a) payments are made before treatment, (b)
corruption or embezzlement of public resources for personal gains, (c) lack of healthcare
facilities, and (d) lack of personnel or doctors in public hospitals. The study’s findings on
Lee’s pull factors for the participants migration to the United States include (a) a
perception of free access to healthcare in emergencies, (b) cheaper health insurance for
undocumented immigrants, and (c) quality healthcare services. The implication of the
findings for social change is to enlighten us about the relationship between healthcare
access and migration and provide useful information for Hidalgo County local health
authorities and United States Immigration policy setters to better guide debate on public
healthcare policies. The U.S. government would be well served to spend time to clear
some misconception that emergency healthcare is “free”. Finally, the information that
availability of jobs and family reunion as primary pull factors of immigration to the
United Sates should be used by immigration legislators in the United States to help guide
debate on immigration policies.

220
References
Alden, E. (2017). Is border enforcement effective? What we know and what it means.
Journal on Migration and Human Security, 5(2), 481-490.
https://journals.sagepub.com/doi/pdf/10.1177/233150241700500213
Allyn, B. (2019). California is 1st state to offer health benefits to adult undocumented
immigrants. NPR. https://www.npr.org/2019/07/10/740147546/california-
firststate-to-offer-health-benefits-to-adult-undocumented-immigrants
America College of Emergency Physicians (n.d.). EMTALA fact sheet.
https://www.acep.org/life-as-a-physician/ethics--legal/emtala/emtala-fact-sheet/
American Hospital Association. (2021, February 28). AHA pushes back on RAND report
on hospital pricing. https://www.aha.org/news/news/2021-02-18-aha-pushesback-
rand-report-hospital-pricing
Artiga, S., & Diaz, M. (2019). Health coverage and care for undocumented Immigrants.
Kaiser Family Foundation. https://www.kff.org/racial-equity-and-
healthpolicy/issue-brief/health-coverage-and-care-of-undocumented-immigrants/
Associated Press (2019). Pentagon sending more troops to southwest border.
https://apnews.com/article/27e34a4200a844f7b282ee7e9b7f97c6
Baltagi, B. H., Lagravinese, R., Moscone, F., & Tosetti, E. (2017). Health care expenditure
and income: a global perspective. Health economics, 26(7), 863-874.
https://www.econstor.eu/bitstream/10419/147345/1/cesifo1_wp6091.pdf
Baranowski, K. A., & Smith, L. (2018). Working with undocumented immigrants from
Mexico: Experiences of practitioners in New Mexico and Texas. Professional
Psychology: Research and Practice, 49(3), 185–

221
192. https://doi.org/10.1037/pro0000191
Betancourt, T. S., Abdi, S., Ito, B. S., Lilienthal, G. M., Agalab, N., & Ellis, H. (2015).
Focus group qualitative interview protocol for Somali Refugees.
https://doi.org/10.1037/t38771-000
Black, A. E. (2005). The separation and reunification of recently immigrated Mexican
families [Doctoral Dissertation, Walden University]. ProQuest.
https://search.proquest.com/openview/7076314f5bbd2356866e2acf84af5d0d/1?pq
-origsite=gscholar&cbl=18750&diss=y
Borjas, G. J. (2019). Immigration and economic growth. National Bureau of Economic
Research Working Paper Series, (w25836).
https://www.nber.org/system/files/working_papers/w25836/w25836.pdf
Boston University. (n.d). Qualitative data analysis software comparisons. Boston
University Information Services & Technology Home.
https://www.bu.edu/tech/services/support/desktop/distribution/nvivo/comparison
Budiman, A. (2020). Key findings about U.S. immigrants. Pew Research.
https://www.pewresearch.org/fact-tank/2020/08/20/key-findings-about-u-
simmigrants/
Castaneda, R. (2016). Where can undocumented immigrants go for health care? U.S.
News & World Report. https://health.usnews.com/wellness/articles/2016-11-
02/where-can-undocumented-immigrants-go-for-health-care
Connor, P. (2013). 5 challenges to estimating global migration. Pew Research Center.

222
https://www.pewresearch.org/fact-tank/2013/10/25/5-challenges-to-
estimatingglobal-migration/
Connor, P. (2016). International migration: Key findings from the U.S., Europe and the
world. Pew Research Center.
https://www.pewresearch.org/facttank/2016/12/15/international-migration-key-
findings-from-the-u-s-europe-andthe-world/
Connor, P., López, G. (2016). 5 facts about the U.S. rank in worldwide migration. Pew
Research Center. https://www.pewresearch.org/fact-tank/2016/05/18/5-factsabout-
the-u-s-rank-in-worldwide-migration/
Creswell, J. (2007). Qualitative inquiry and research design: Choosing among five
approaches (2nd ed.). Thousand Oaks, CA: Sage Publications.
Creswell, J. (2009). Research design: Qualitative, quantitative, and mixed methods
approaches (3rd ed.). Thousand Oaks, CA: Sage Publications.
Davis, R. C., & Erez, E. (1998). Immigrant populations as victims: Toward a multicultural
criminal justice system. US Department of Justice, Office of Justice Programs,
National Institute of Justice.
https://play.google.com/store/books/details?id=eYHaAAAAMAAJ&rdid=book-
eYHaAAAAMAAJ&rdot=1
Denzin, N. K., & Lincoln, Y. S. (2008). Strategies of qualitative inquiry (3rd ed.).
Thousand Oaks, CA: Sage Publications.
Desilver, D. (2019). Immigrants don’t make up a majority of workers in any U.S.

223
industry. Pew Research Center.
https://www.pewresearch.org/facttank/2017/03/16/immigrants-dont-make-up-a-
majority-of-workers-in-any-u-sindustry/
Faridi, R. (2018). Theories of migration.
https://rashidfaridi.com/2018/04/05/migrationtheories-lees-push-pull-theory/
Flavin, L., Zallman, L., McCormick, D., & Wesley Boyd, J. (2018). Medical expenditures
on and by immigrant populations in the United States: a systematic review.
International Journal of Health Services, 48(4), 601-621.
https://www.researchgate.net/profile/J_Wesley_Boyd_MD_PhD/publication/3269
04334_Medical_Expenditures_on_and_by_Immigrant_Populations_in_the_Unite
d_States_A_Systematic_Review/links/5ea62bc145851553fab2cb30/Medical-
Expenditures-on-and-by-Immigrant-Populatio
Gramlich, J. (2019). How Americans see illegal immigration, the border wall and political
compromise. Pew Research Center.
https://www.pewresearch.org/facttank/2019/01/16/how-americans-see-illegal-
immigration-the-border-wall-andpolitical-compromise/
Gubernskaya, Z., & Dreby, J. (2017). US immigration policy and the case for family
unity. Journal on Migration and Human Security, 5(2), 417-430.
https://journals.sagepub.com/doi/pdf/10.1177/233150241700500210
Guerra, G., Gutiérrez-Calderón, E., Salgado de Snyder, N., Borja-Aburto, V. H., Martínez-
Valle, A., & González-Block, M. Á. (2018). Loss of job-related right to healthcare
224
associated with employment turnover: challenges for the Mexican health system.
BMC Health Services Research, 18(1), Article 457.
https://doi.org/10.1186/s12913-018-3283-7
Hall, D. (2010). A phenomenological inquiry of chronic homeless individuals’ challenges
to independence [Doctoral dissertation, Walden University]. ProQuest.
https://scholarworks.waldenu.edu/cgi/viewcontent.cgi?article=1818&context=diss
ertations
Heslin, B. (2018). Overstays: The lesser-known illegal immigration issue [Master’s thesis,
Naval Post Graduate School, Monterey, California]. Homeland Security
Affairs. https://www.hsaj.org/articles/14957
Hoekstra, M., & Orozco-Aleman, S. (2017). Illegal immigration, state law, and deterrence.
American Economic Journal. Economic Policy, 9(2), 228-252.
http://doi.org/10.1257/pol.20150100
Hone, T., & Gómez-Dantés, O. (2019). Broadening universal health coverage for children
in Mexico. The Lancet. Global Health, 7(10), e1308–e1309.
https://doi.org/10.1016/S2214-109X(19)30312-2
Hynes, V. (2013). United Nations general assembly adopts universal health care
resolution. CMAJ: Canadian Medical Association Journal, 2, 107.
Inés Ospina, G. (2019). The Illegal Immigration Flows to the Southern Border of the
United States of America. UNISCI Discussion Papers, 50, 169–189.
https://doi.org/10.31439/UNISCI-54

225
Jacob, S. A., & Furgeson, S. P. (2012). Writing interview protocols and conducting
interviews: Tips for students new to the field of qualitative research. The
Qualitative Report, 17(42), 1-10.
http://nsuworks.nova.edu/cgi/viewcontent.cgi?article=1718&context=tqr
Justice for Immigrants (2017). Pull and pull factors of immigration. Justice for
Immigrants. https://justiceforimmigrants.org/what-we-are-
workingon/immigration/root-causes-of-migration/
Kerwin, D. (2018). From IIRIRA to Trump: Connecting the Dots to the Current US
Immigration Policy Crisis. Journal on Migration and Human Security, 6(3), 192–
204. https://doi.org/10.1177/2331502418786718
Krogstad, J., M. (2020). Americans broadly support legal status for immigrants brought to
the U.S. illegally as children. Pew Research Center.
https://www.pewresearch.org/fact-tank/2020/06/17/americans-broadly-
supportlegal-status-for-immigrants-brought-to-the-u-s-illegally-as-children/
Kuruvilla, R., & Raghavan, R. (2014). Health care for undocumented immigrants in
Texas. Texas Medicine. https://www.texmed.org/July14Journal/
Lee, E. (1966). A theory of migration. Demography, 3(1), 47-57.
https://doi.org/10.2307/2060063
Lee, S. (2019). Family separation as slow death. Columbia Law Review, 119(8), 2319-
2384.
https://www.immigrationresearch.org/system/files/Family%20Separation%20as%
20Slow%20Death.pdf

226
Lincoln, Y. S., & Guba, E. G. (1985). Naturalistic inquiry. Beverly Hills, CA: Sage
Publications.
Macías-Rojas, P. (2018). Immigration and the war on crime: Law and order politics and
the illegal immigration reform and immigrant responsibility act of 1996. Journal
on Migration and Human Security, 6(1), 1-25.
https://doi.org/10.1177/233150241800600101
Manzanares Rivera, J. L. (2017). Does the border matter for health care? A study of
medical services provider’s location at cities in the Mexican side of the border.
Estudios Fronterizos, 18(36), 151–168.
https://doi.org/10.21670/ref.2017.36.a07
Martinez, O., Wu, E., Sandfort, T., Dodge, B., Carballo-Dieguez, A., Pinto, R., ... &
Chavez-Baray, S. (2015). Evaluating the impact of immigration policies on health
status among undocumented immigrants: a systematic review. Journal of
immigrant and minority health, 17(3), 947-970. https://doi.org/10.1007/s10903-
013-9968-4
Martínez-Martínez, O. A., & Rodríguez-Brito, A. (2020). Vulnerability in health and
social capital: a qualitative analysis by levels of marginalization in Mexico.
International Journal for Equity in Health, 19(1), Article 1.
https://doi.org/10.1186/s12939-020-1138-4
Mason, M. (2010). Sample size and saturation in Ph.D. studies using qualitative
interviews. Forum Qualitative Sozialforschung/Forum: Qualitative Social
Research, 11(3), article 8. http://www.qualitative-research.net/index.php/fqs
Massey, D. S. (1999). Why does immigration occur?: A theoretical synthesis (pp. 34-52).

227
eportfolios.macaulay.cuny.edu/pony2014shama/files/2014/02/Kaczmarczyk_Rea
ding-1.pdf
McNabb, D. E. (2008). Research methods in public administration and nonprofit
management: Quantitative and qualitative approaches (2nd ed.). Armonk, NY: M.
E. Sharpe, Inc.
Miles, M. B., Huberman, A. M., & Saldana, J. (2014). Qualitative data analysis: A
methods sourcebook (3rd ed.). Thousand Oaks, CA: SAGE.
Moustakas, C. (1994). Phenomenological research methods. Thousand Oaks, CA: Sage
Publications.
Murtaza, F. A. (2020). Causes and Effects of International Migration. Annals of the
University of Craiova, Economic Sciences Series, 2(48), 146–155.
Muschek, A. G. (2015). The impact of undocumented immigrants on the healthcare
infrastructure of the United States. The Journal of Social, Political, and Economic
Studies, 40(4), 329-367. https://doi.org/docview/1774914980?fromopenview=true
Orrenius, P., & Zavodny, M. (2019). Do immigrants threaten U.S. public safety? Journal
on Migration and Human Security, 7(3), 52-61.
https://doi.org/10.1177/2331502419857083
O’Sullivan, E., Rassel, G. R., Berner, M., & Taliaferro, J. D. (2017). Research methods for
public administrators (6th ed.). New York, NY: Routledge
Parry, S. (2019). Immigration. Britannica Kids.
https://kids.britannica.com/scholars/article/immigration/600943
228
Passel, J. S., & Cohn, D. (2019). Unauthorized immigrant population. Pew Research
Center. https://www.pewresearch.org/fact-tank/2019/06/12/us-
unauthorizedimmigrant-population-2017/
Patton, M. Q. (2015). Qualitative research & evaluation methods: Integrating theory and
practice (4th ed.). Thousand Oaks, CA: SAGE
Pelcastre-Villafuerte, B. E., Meneses-Navarro, S., Ruelas-González, M. G.,
ReyesMorales, H., Amaya-Castellanos, A., & Taboada, A. (2017). Aging in rural,
indigenous communities: an intercultural and participatory healthcare approach in
Mexico. Ethnicity & Health, 22(6), 610–630.
https://doi.org/10.1080/13557858.2016.1246417
Pierce, S. (2019). Immigration-related policy changes in the first two years of the Trump
administration. Washington, DC.: Migration Policy Institute.
https://www.migrationpolicy.org/sites/default/files/publications/ImmigrationChan
gesTrumpAdministration-FinalWEB.pdf
Pietkiewicz, I., & Smith, J. (2012). A pratical guide to using interpretative
phenomenological analysis in qualitative research psychology. Psychological
Journal, 20(1), 7-14. doi:10.14691/CPPJ.20.1.7
Predictive Analysis Today. (2016a). Top 15 qualitative data analysis software. Boston
University Information Services & Technology Home.
https://www.bu.edu/tech/services/support/desktop/distribution/nvivo/comparison/
Ravitch, S. M., & Carl, N. M. (2016). Qualitative research: Bridging the conceptual,
theoretical, and methodological. Sage Publications

229
Rivera-Hernández, M., Rahman, M., & Galárraga, O. (2019). Preventive
healthcareseeking behavior among poor older adults in Mexico: the impact of
Seguro
Popular, 2000-2012. Salud Publica de Mexico, 61(1), 46–53.
https://doi.org/10.21149/9185
Roberts, B. W. (2017). Illegal immigration outcomes on the U.S. southern border. The
Cato Journal, 3, 555.
Rubin, H. J., & Rubin, I. S. (2012). Qualitative interviewing: The art of hearing data (3rd
ed.). Thousand Oaks, CA: Sage Publications
Rueben, K. S., & Gault, S. (2017). State and local fiscal effects of immigration. Urban
Institute.
http://www.urban.org/sites/default/files/publication/90796/state_and_local_fiscal_
effects_of_immigration.pdf
Rudestam, K. E., & Newton, R. R. (2007). Surviving your dissertation: A comprehensive
guide to content and process (3rd ed.). Thousand Oaks, CA: Sage Publications,
Inc.
Sawyer, N. (2017). Why the EMTALA mandate for emergency care does not equal
healthcare “coverage”. West Jem. https://doi.org/10.5811/westjem.2017.5.34826
Sharma, G. (2017). Pros and cons of different sampling techniques. International journal
of applied research, 3(7), 749-752.
https://d1wqtxts1xzle7.cloudfront.net/58765080/Pros_and_cons_of_sampling.pdf

230
?1554128717=&response-
contentdisposition=inline%3B+filename%3DImpact_Factor_5_2_IJAR.pdf&Expi
res=16
11465834&Signature=D2Bz8lKJr12iEeu9Hu~JMsyqELlj6iX6JnM5BDUdT2nGa
y1Z-i9wfmX0YcJR
Shenton, A. K. (2004). Strategies for ensuring trustworthiness in qualitative research
projects. Education for Information 22(2), 63-75.
Sloan, A., & Bowe, B. (2014). Phenomenology and hermeneutic phenomenology: The
philosophy, the methodologies, and using hermeneutic phenomenology to
investigate lecturers’ experiences of curriculum design. Quality &
Quantity, 48(3), 1291-1303.
http://citeseerx.ist.psu.edu/viewdoc/download?doi=10.1.1.1001.2798&rep=rep1&
type=pdf
Sosa, R. S. G., & Sosa-Rubí, S. G. (2016). Is being insured sufficient to ensure effective
access to health care among poor people in Mexico in the long term? Health
Services Research, 51(4), 1319–1322. https://doi.org/10.1111/1475-6773.12541
Waldinger, R., Popkin, E., & Magana, H. A. (2008). Conflict and contestation in the cross-
border community: Hometown associations reassessed. Ethnic and Racial
Studies, 31(5), 843-870.
https://escholarship.org/content/qt2r8674q3/qt2r8674q3.pdf

231
Wood L. (2018). Impact of punitive immigration policies, parent-child separation and
child detention on the mental health and development of children. BMJ paediatrics
open, 2(1), e000338. https://doi-org.org/10.1136/bmjpo-2018-000338
Wurie, C. M. (2012). Exploring the Lives of Salvadoran Families After the
Implementation of Illegal Immigration Reform and Immigrant Responsibility Act
of 1996 section 287 (g) [Doctoral dissertation, Walden University]. ProQuest.
https://search.proquest.com/openview/b214138a52887e2531c07254273d3030/1?p
q-origsite=gscholar&cbl=18750&diss=y

