


Running head: QUESTION SET TWO BUDGET VARIANCES 1
Question Set Two: Budget Variances
Tessa Hartsell
Liberty University

QUESTION SET TWO: BUDGET VARIANCES
QUESTION SET TWO
Budget Variances
1. Why is it important for a nurse leader to understand variance reporting? How does this
reporting become a valuable tool?
“A variance report is a summary of the major exceptions to the budget during a
given time frame and an explanation of why the exceptions occurred” (Liberty, 2015). It is
important for managers to understand the variance report because it provides opportunities to
both understand control the variances in the budget. The nurse manager must recognize the
variances so that she/he can involve the staff so that they can be a part of the process of
controlling cost to stay within budget. The more the manager involves and informs her staff of
the areas of concerns, even within the budget, the more she empowers them and working
together the solution and process will likely be more successful. While the budget may be the
managers responsibility, I believe it is also her responsibility to communicate to her staff overall
budget information and the variances. For example, it is important for staff to understand how
overtime can become a variance in the budget. Working together to stay within budget and
looking and brainstorming ways to cut down on variance within the budget can be a job of
everyone.
2. Staffing is usually the most expensive resource in the provision of care. What reports
would provide the nurse leader with valuable information regarding this expense?
As stated above staffing is often the most expensive resource in the provision of care, it is
important for the nurse leader to know her staffing and man-hours and to know which report
gives her the most accurate information. Bi-weekly FTE reports are usually the most accurate at
2

QUESTION SET TWO: BUDGET VARIANCES
showing individual employee hours and/or man-hours or FTEs broke down by job classification
(Liberty, 2015). This report lists employees by name, their classification, as well as productive,
nonproductive, overtime FTEs. It provides the nurse leader a tracking report to show where
employee’s time is being spent. This report should be analyzed to make sure that the most
expensive resource on the budget is being managed and used appropriately. The bi-weekly report
is far superior with providing this information than the monthly operations report because it
typically does not include a break down of man-hours.
3.As a nurse manager of your unit, why is it important to keep track of education, meeting,
and orientation hours?
As a nurse manager it is important to track how hours are spent including education,
orientation, and meeting hours. There are constant changes in healthcare, whether it is related to
evidence-based practices that guide a change in practice, change in process and procedures, or
implementation of new electronic medical records we are always undergoing change. It is
important for new employees and existing employees to be oriented to these changes. The time
spent must be tracked and reported because it is hours worked; yet not providing direct care in
the form of productive man-hours. It is important to show education is encouraged and provided
to show that competency is maintained. In addition, the employees while at work are not
providing care to patients so other employees are often covering their job. It is important to be
able to show why man-hours increase as well as overtime. It is also important to keep track of
education and orientation hours so that it can be budgeted and compared to previous years.
3

QUESTION SET TWO: BUDGET VARIANCES
4. What resource is available for the nurse leader to identify reimbursement for Medicare
and Medicaid patients?
Medicare sets the rate of reimbursement for the services provided and the rate is often
less than what private insurance pays. It also differs based on the location of service such as
acute care hospital, long-term care facility, and home health services. “Medicare, reimburses by
an assigned DRG code or an assigned RUG, with a fixed dollar amount for all services provided
during the hospital or skill care stay” (Liberty, 2015). DRG stands for diagnosis-related group
and RUG is for resource utilization group.
The nurse manager should be aware of the patient and the patient’s payer source mix to
understand the different variance in reimbursement. These reimbursements are subject to be
adjusted annually. I believe it is important for the nurse manager to make himself or herself
aware of the potential change in reimbursement every year. In addition, it is also extremely
important to be aware of the factors that could impact reimbursements such as level of care not
being achieved, never events occurring, and one of the biggest is 30-day readmission after
discharge. As our text states, “Nurse managers have a key role in avoiding this lost of
reimbursement” (Liberty, 2015). I know that 30-readmission is a hot topic at my place of
employment and a number of processes are being implemented to recognize the patients at high
risk for readmission and to educate and put systems in place to help to avoid readmissions.
5. Why do freestanding skilled nursing facilities function more profitably than skilled
nursing facilities in acute care organizations?
Freestanding skilled nursing facilities likely function more profitably due to not as much
overhead cost as skilled nursing facilities in acute care organizations. In addition, freestanding
4

QUESTION SET TWO: BUDGET VARIANCES
facilities may not care for patients that require as much intense therapy and nursing care. The
therapy can be more intense, typically three hours or more a day in the skilled nursing facilities
in the acute care setting.
6. What is a cost-to-charge ratio? Why should a nurse leader understand this ratio, and
how would he or she utilize it?
A cost-to-charge ratio is a cost determination method that was specified by Medicare to
report annual cost. Today, most hospitals have adopted this method as the primary source of all
hospital cost and cost accounting information. This report is referred to as the Medicare Cost
Report and is used by CMS to calculate and update reimbursement rates. The Healthcare Cost
Report Information System is publicly reported data available to the public for review; in
addition healthcare agencies also view this information to benchmark their cost and performance
compared to their competitors. (Liberty, 2015).
The nurse manager should understand this ratio provides useful information however it
can be misinterpreted because it does not allow for a full assessment of true revenue production
of a particular service, because if the healthcare agency is profitable as a whole then it is
assumed that all service areas are profitable, which may not be the case. (Liberty, 2015). It is
important that the nurse manager may not get an accurate vision of the profitability of a service
with the CCR cost determination method. The nurse manager should use the CCR method to
compare its agencies results to others and to see the areas of strength. However, I do believe it is
important to look at all service areas to ensure that it is as productive as possible to ensure profit
is achieved.
5

QUESTION SET TWO: BUDGET VARIANCES
7. What are the top ten diagnosis-related groups (DRGs) in your organization? Has the
administrative team determined if each is cost effective? Is this accurate? If not, how would
you determine whether they are cost effective?
After speaking with our Director of Financial Services, I learned that hospice does not
use DRGs, as hospitals do. In addition, our reimbursement is not based on diagnosis. However, it
is important to show a case mix of patient with different diagnosis and location that hospice
service is provided such as home care, skilled nursing facilities, assisted living center, and our
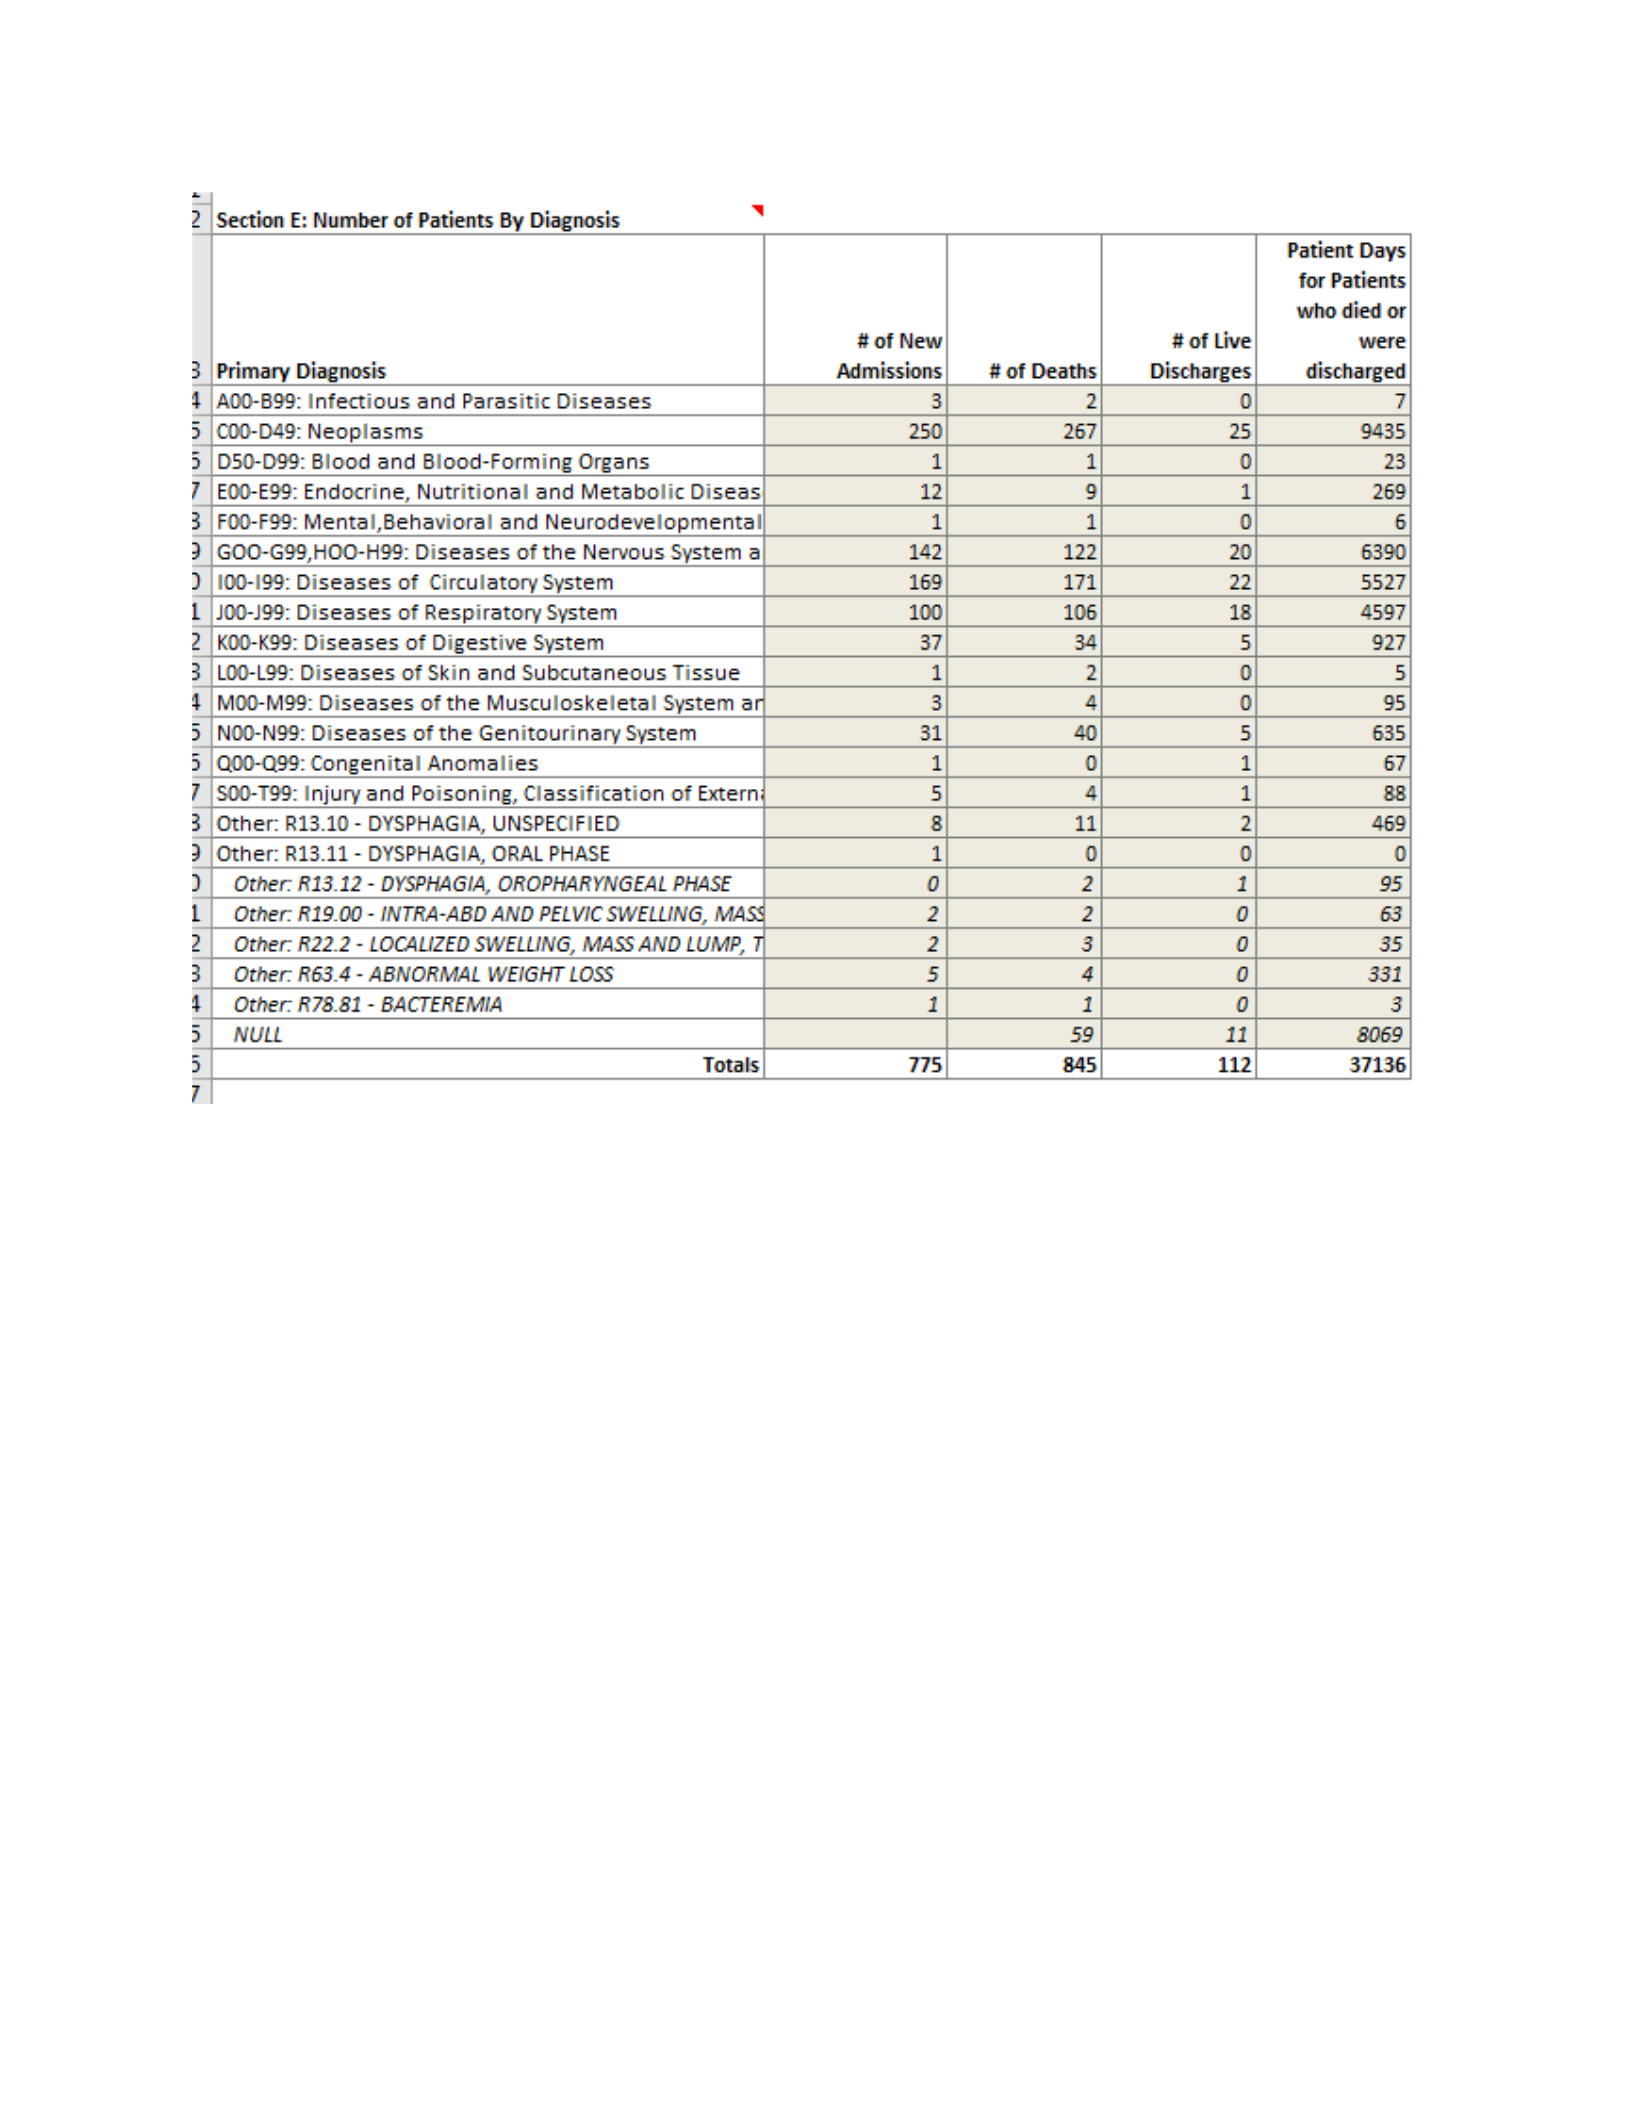
hospice house. As you can see from the chart below our top four diagnosis include neoplasms,
disease of the circulatory system, disease of the nervous system, and disease of the respiratory
system make up well over half of our patient population.
While we do not use DRGs, certain diagnosis are more costly than others. Often time
neoplasm is one of the most costly diagnoses due to the medication management that is
associated with the patient’s pain. Respiratory diseases can also be costly due to medications.
Alzheimer’s disease which is our third most common diagnosis is less expensive and do not
require as much resources, the biggest focus with this diagnosis is safety concerns, including
falls that can become costly. While neoplasm is our top diagnosis and can be the costly
diagnosis, it averages out fairly well. The first several weeks after admission are costly with this
time often being spend with pain management requiring extra visits and resources. Often during
the middle of the patient hospice stay the resources are not as demanding until closer to death
where often times pain levels either increase steady, remain steady and palliated with current
medication, and occasionally the pain will disappear.
6
QUESTION SET TWO: BUDGET VARIANCES
8. In the new value-based reimbursement environment, what other measures can a nurse
leader take to enhance reimbursement and prevent revenue loss?
I am a supporter of the value-based reimbursement; I believe this brings the care and the
quality of care back to the patient. It focuses on patient outcomes. However it does have it’s
faults as well as does any reimbursement system. The nurse manager can play a pivotal role to
enhance reimbursement and prevent revenue loss. The nurse manager should communicate
frequently to his or her staff that the goal is to provide the highest level of care to the patient.
Placing the focus on patient needs and safety.
Not meeting specified care requirements, never events occurring, and patients being
readmitted within 30-days are all ways that reimbursement can be lost. A never event is a serious
medical error or adverse event that should never happen i.e. hospital-acquired pressure ulcer, or
7

QUESTION SET TWO: BUDGET VARIANCES
wrong site surgery. “For every 100 patient discharges with a pressure ulcer, the approximate loss
of hospital revenue is $105,556; however, the range of preventable cost is $176,450 to
$2,646,550” (McKeon & Cardell, 2011). This is a huge hit in loss of revenue. I believe that
through education these things can be prevented. It is important to educate staff that pressure
ulcers not only affect the patient it affects revenue as well, and these preventable incidents
should never occur.
Another primary area of focus should be on readmission within 30 days. I know this is a
big focus within Carolinas Health Care System. I am with CHS hospice and palliative care
program and one of our hospitals that is in a small rural area was seeing a higher number of
readmission compared to all of our other hospitals. These larger hospitals have more resources in
nurse educators, palliative care, and hospice transition coordinators. I was part of a needs
assessment for this rural hospital with one of the primary goals was to reduce readmissions. We
made our proposal and the Advance Illness Resource (AIR) role was implemented. This role’s
goal is to serve as a resource to patients with advance/chronic illnesses. Some of the resources I
provide include education on the patient’s chronic illness, goals of care conversation to ensure
the treatment being provided aligns with patient and families goal, education on NC MOST
forms, advance directives education and assistance in completing, as well as hospice and
palliative care education. Within the fourteen months this role has been active we have seen a
40% reduction in readmissions.
So that leads me back to my greatest belief is communication and education. The nurse
manager must educate on things that negatively effects reimbursement and loss of revenue. Our
job as nurses is to educate this includes educating our patients and our peers. Focusing on
8

oF
QUESTION SET TWO: BUDGET VARIANCES
eliminating never events, that the appropriate quality care is provided to every patient every time,
and doing your part in empowering and educating the patient to help prevent readmissions.
9

QUESTION SET TWO: BUDGET VARIANCES
Reference
Liberty University. (2015). NURS 523: Financial and resource management for nurse leaders
(Custom 3rd ed.). Burlington, MA: Jones & Bartlett Learning. ISBN: 9781284005127.
McKeon, L., & Cardell, B. (2011). Preventing never events: What frontline nurses need to
know : Nursing made Incredibly Easy. Retrieved August 2, 2018, from
https://journals.lww.com/nursingmadeincrediblyeasy/Fulltext/2011/01000/Preventing_ne
ver_events__What_frontline_nurses.10.aspx
10

