



1
COST MANAGEMENT
Financial Exercise Assignment:
Cost Management
Jasmine Yumiaco-Marsh
Liberty University
NURS 523: Financial and Resource Management for Nurse Leaders
Dr. Tracey Turner
June 4, 2023
Author Note
Jasmine S. Yumiaco-Marsh
I have no known conflict of interest to disclose.
Correspondence concerning this article should be addressed to Jasmine S. Yumiaco-
Marsh.

2
COST MANAGEMENT
1. Basic cost concepts provide essential knowledge needed for nursing leaders. Discuss the cost per
service unit as it pertains to your area of responsibility. How does this impact the entire organization?
What is the impact of direct and indirect costs? Fixed and variable costs? Full cost versus average
costs? What is the relevant range?
As an assistant nurse manager in Labor & Delivery and Maternal and Newborn unit, knowing
basic cost concepts can provide nurse leaders the knowledge to make the appropriate decisions for the
staff, patients, unit, and organization. According to Jones et al. (2019), a service unit measures a product
or service provided by an organization and can include the length of stays (LOS) measured in hours or
days or the length of surgery or procedure in hours. My area of responsibility falls within L&D and the
postpartum or mom-and-baby unit. The service unit within my department follows the
recommendation of the World Health Organization (WHO). It is measured in patient days, typically from
one to two days for a vaginal delivery and 2 to 4 days for cesarean delivery (Ikeda et al., 2021). However,
several factors can affect the LOS, such as complications and the infant's health.
The better understanding that a leader has regarding the cost per patient day can make an
organization more successful. For example, moms and babies who are provided the necessary care but
stay the minimum days required will be favorable as it cuts overall costs, from supplies, care, etc. In turn,
this leads to more patients being seen, which means more patients and more revenue coming in. An
organization known for this type of efficiency is Kaiser Permanente, where the usual stay for vaginal
deliveries is one day, and two days for C-sections (Kaiser Permanente, n.d.). However, some outliers stay
less than 24 hours if the mother is multiparous and both mom and baby have no complications or longer
than four days if there are postpartum complications.
According to Jones et al. (2019), direct costs are those specifically related to the costs associated
with a specific unit or department that a manager is responsible for or costs directly related to patient

3
COST MANAGEMENT
care. Direct costs can be reached and include medical supplies, pharmacy supplies, and nursing salaries,
to name a few (Jones et al., 2019). It can vary with changes and fluctuations in patients and services, and
the average daily census (ADC) is an example of this that can affect the direct cost. Since the ADC is
usually captured at midnight, patients who stay the bare minimum can lower the ADC if their bed is not
backfilled with another patient upon discharge. Therefore, lowering potentially lowers the direct cost of
the staff needed for the next shift, medications, ancillary staff, etc.
Indirect costs, on the other hand, are not related to any unit, department, or patient care.
Outside costs assigned to the department, such as marketing, facility maintenance, staff education, and
insurance, are all examples of indirect costs to the unit and may not be fully impacted by the cost per
service unit or ADC. Indirect costs have to be allocated within an organization and benefit the overall
operation of the facility rather than one unit or department (Jones et al., 2019).
In terms of fixed and variable costs, fixed costs do not change regardless of patient volume or
census and the implementation of change, while variable costs do (Jones et al., 2019). This concept can
be seen in my area, with fixed costs being the salary and benefits provided to the staff and variable costs
being all types of supplies and medicine that will increase or decrease depending on the ADC. According
to Jones et al. (2019), full costs are the sum of all direct and indirect costs, while the average cost is the
full cost divided by the volume of service units. Within my area of work, the average cost will then be
the total direct and indirect costs divided by the average number of days patients stay, representing each
patient. In addition, the authors define the relevant range as the “normal range of expected activity for
the responsibility center or organization” that is covered within the budget (Jones et al., 2019, p. 147).
For example, within my work area, the salary of the nurse manager is a fixed cost within the relevant
range of the department budget. However, a steady increase in ADC indicates growth within the unit,
which can drive an increase in fixed costs. This concept can be seen in my department as our birth rates

4
COST MANAGEMENT
have increased from approximately 1400 births in a year five years ago to more than 2000 births in a
year last year. The increase in birth rates corresponded to an increasing trend in ADC that ultimately
showed the need for more staffing to care for the increase in our patient population.
2. The cost to treat patients depends on many variables. One of the variables is volume. The unit you
manage has fixed costs of $575,000 and variable costs per patient day of $450.00. The patient days
equate to 3,500. What is the average cost per patient day?
The variable cost would be the variable costs per patient day of $450.00 multiplied by the
patient days, for a total of $1.575 million. The full or total cost is the fixed cost of $575,000 plus the
variable cost calculated above of $1.575 million, which equals $2.150 million. Lastly, the average cost per
patient day is the total cost of $2.150 million divided by the patient days of 3,500, which equals
approximately $614.29.
3. What are cost estimation techniques? Discuss a technique and provide example(s) of when you as a
nurse leader would choose this approach.
Cost estimation techniques predict future costs and are a relatively complex and integral part of
financial management. My organization utilizes a method that incorporates the unit's historical data
ranging from finances to previous trends and behavior of the patient population. The future estimations
are then compared by these standards in predicting the costs for the next fiscal year. Before COVID, our
birth rates were approximately in the 1400s per year. At the beginning of COVID, the numbers dropped
even more as more mothers chose to deliver at home. However, a year after the start of COVID, our birth
rates started rising again and have continued to rise since and came to be dubbed as COVID babies. This
increase is evident in the steady rise of the average daily census. My organization stayed within the
current method they had in the past, which is regression analysis in conjunction with adjusting costs for
inflation when considering next year's budget.

5
COST MANAGEMENT
4. Break-Even Analysis (BEA) is a technique utilized to find specific volume at which a program or
service neither makes nor loses money. With the formula provided in your textbook/assigned
readings, provide an example (hypothetical or from your personal experience) that demonstrates this
technique. Discuss the relationship between revenue and expenses. Was the program or service
profitable or depict a loss?
Something relatively new that has been implemented for our postpartum mothers who
delivered via C-section is physical therapy (PT). I wonder why PT was never part of the enhanced
recovery after surgery (ERAS) program, as it is a major abdominal surgery regardless if our patient
population are relatively healthier and younger women. Based on this new implementation,
approximately 25% of deliveries are via direction due to the high-risk patients we see as we are a Fetal
Care and Treatment and an Accreta, Increta, and Percreta center. According to Forbes, the average cost
of seeing a PT in an inpatient setting ranges from $400 to $500 (Baluch, 2023). The average cost for this
exercise will be $450 per patient, where approximately 500 c-section patients will be seen. The fixed cost
of providing physical therapy is $25000, and the variable cost for visiting new C-section mothers is $200.
To find the BEA, the cost of PT must be subtracted from the variable cost ($450-$250), which must then
be used to divide the fixed cost by it ((25000)/(450-250)). The result is 125 patient visits from PT are
required to break even with this program.
5. How would you determine the staffing mix for an inpatient unit?
According to Jones et al. (2019), staffing mix has always been an issue in any organization due to
the varying patient classification systems and the need to specify the hours needed by staff type. It
considers the required hours but does not specify the mix of care needed or provided. The staffing mix
is constantly an issue in my unit. As a hospital with a primary care nursing model, we do not have any
aids, assistants, or technicians to assist with daily cares. The nurses are responsible for all aspects of care
6
COST MANAGEMENT
for their patients. Our staffing mix is always tricky due to the different skills needed per shift for our
various patient populations on the floor. On any given day, we need nurses who are trained in medical-
surgical, postpartum/couplet care, normal newborn nursery for baby-specific tasks and tests, advanced
neonatal resuscitation nursery to catch and recover babies, antepartum, labor and delivery, scrub in the
OR, circulate in the OR, recover in PACU, admit and triage in triage, and lastly, be a charge nurse. The
staffing variable has always been an issue because the acuity tool used in our organization does not
accurately depict the acuity of our laboring patients. Our acuity system requires documenting the acuity
of the patients prospectively. However, this type of system makes it nearly impossible to accurately
capture our laboring patients as it is hard to predict what could happen in a delivery. Instead, my unit
staffs for the next shift according to the Association of Women's Health, Obstetric, and Neonatal Nurses
(AWHONN) or state guidelines. Although we tend to lean more toward the AWHONN guidelines because
they offer a better patient-to-nurse ratio due to the high-risk patients we see.
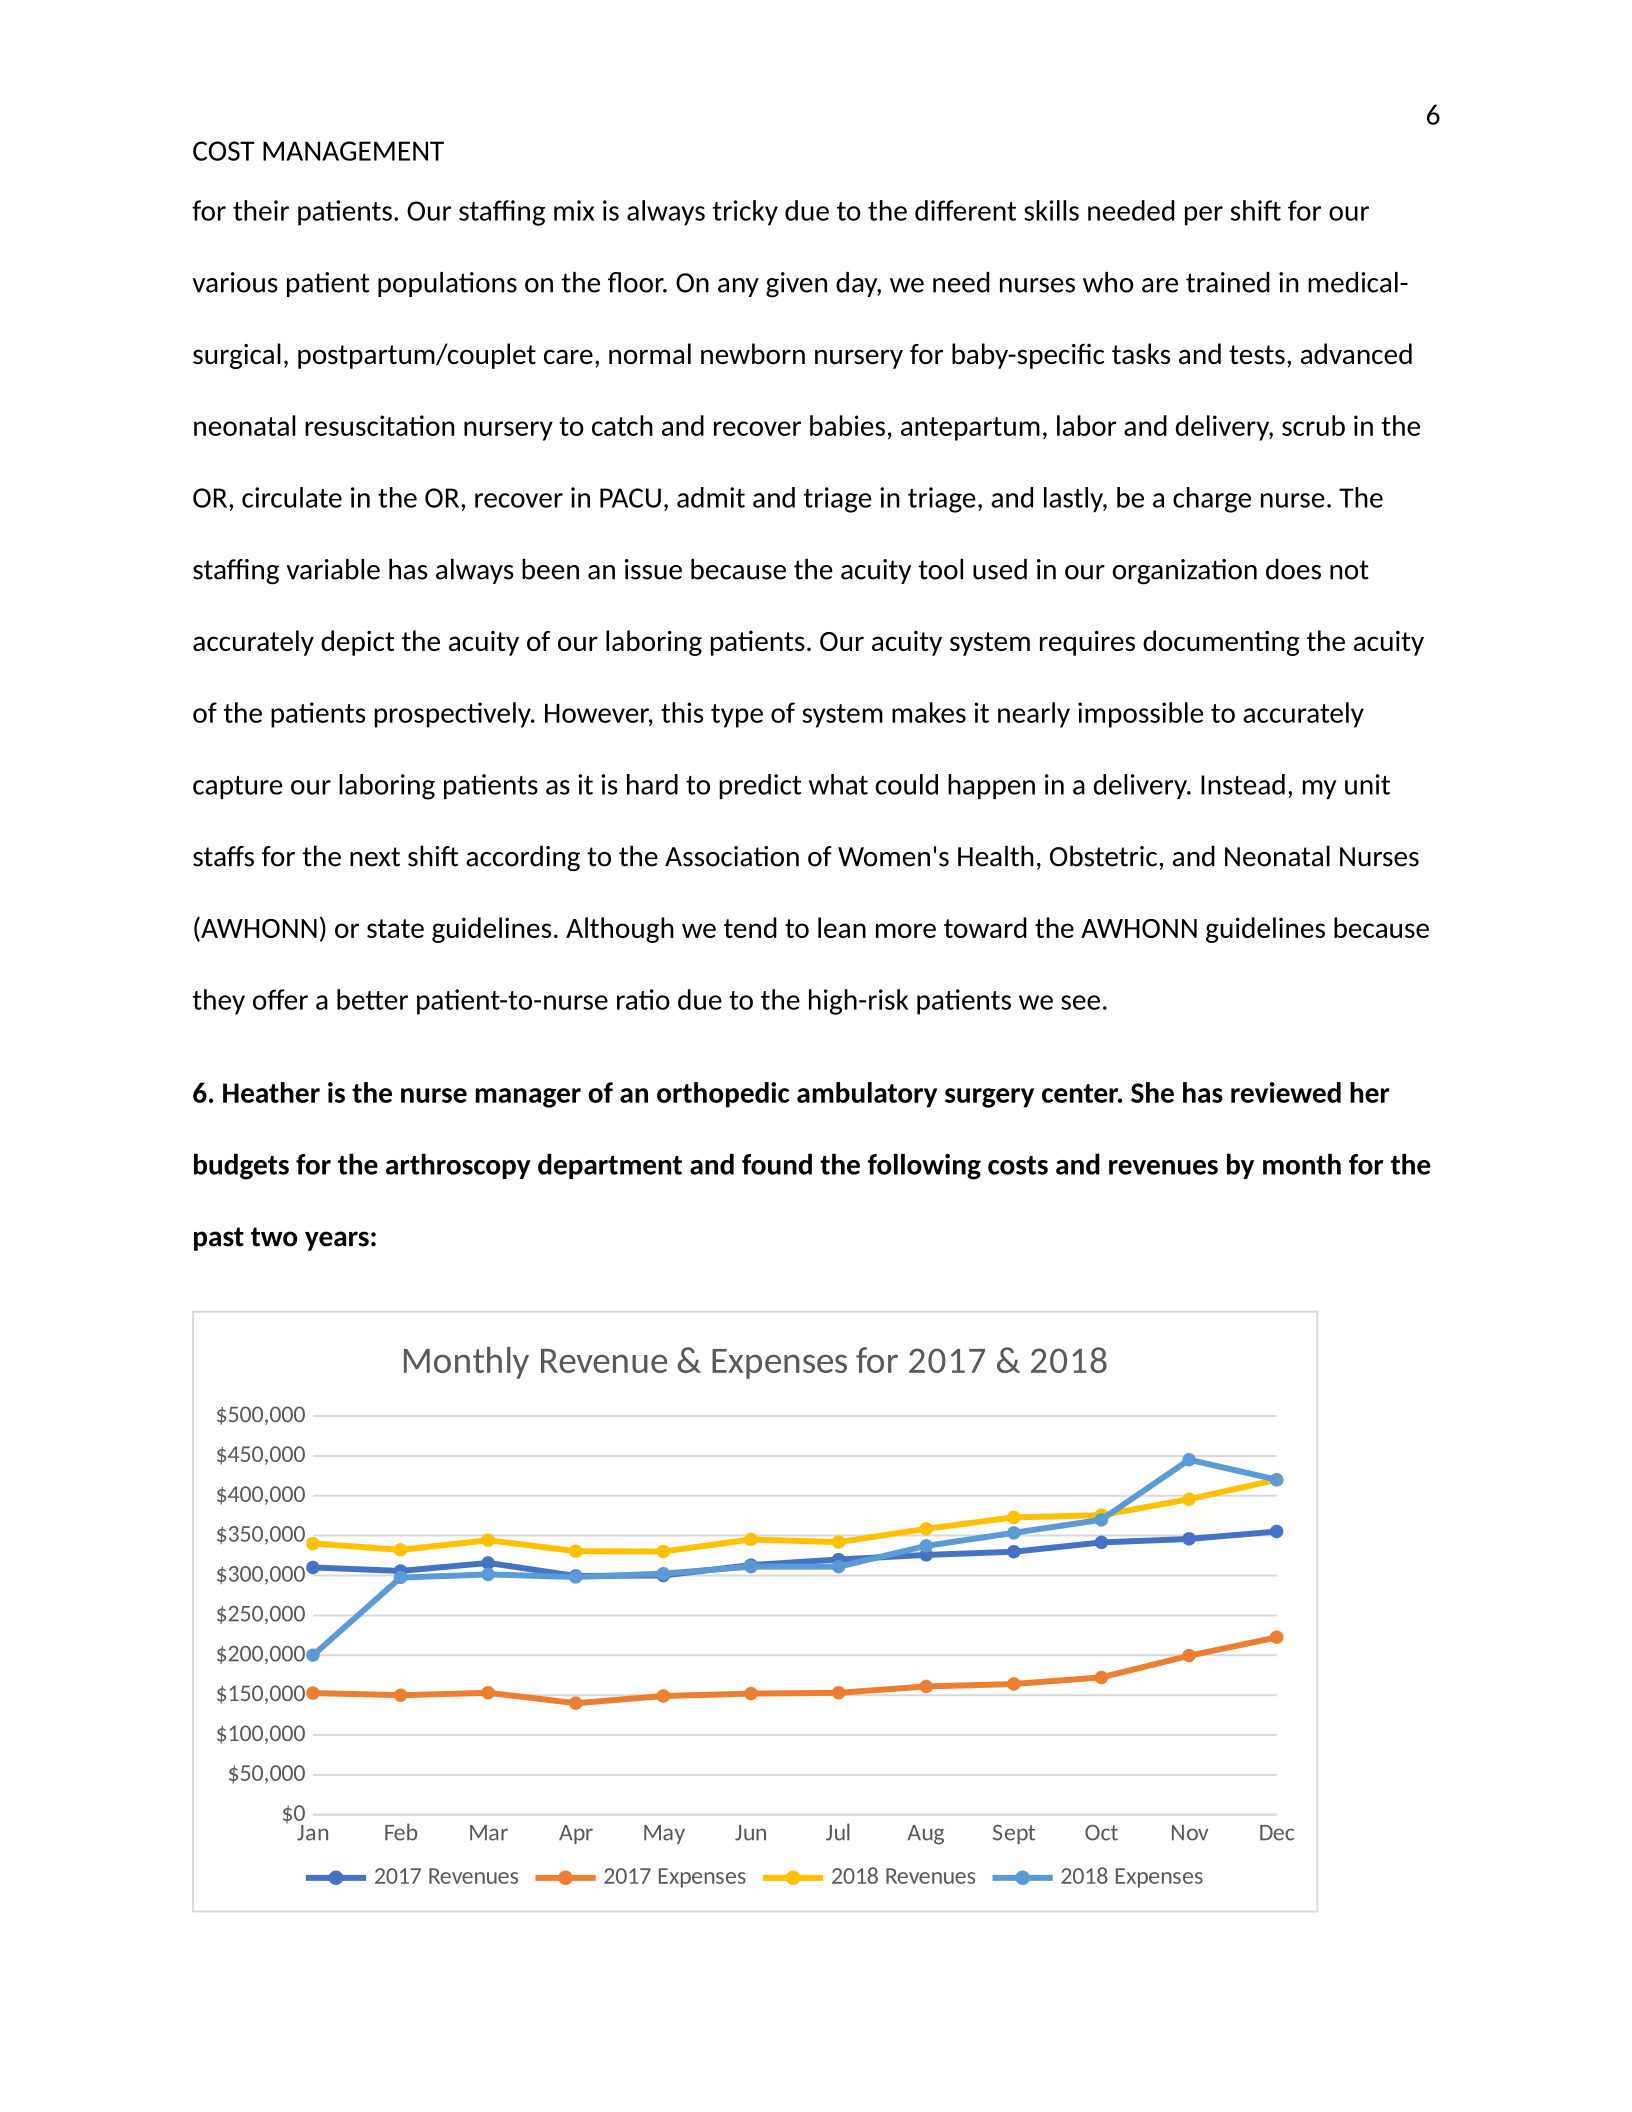
6. Heather is the nurse manager of an orthopedic ambulatory surgery center. She has reviewed her
budgets for the arthroscopy department and found the following costs and revenues by month for the
past two years:
Jan Feb Mar Apr May Jun Jul Aug Sept Oct Nov Dec
$0
$50,000
$100,000
$150,000
$200,000
$250,000
$300,000
$350,000
$400,000
$450,000
$500,000
Monthly Revenue & Expenses for 2017 & 2018
2017 Revenues 2017 Expenses 2018 Revenues 2018 Expenses
7
COST MANAGEMENT
Totals
$0
$500,000
$1,000,000
$1,500,000
$2,000,000
$2,500,000
$3,000,000
$3,500,000
$4,000,000
$4,500,000
$5,000,000
Total Revenues & Expenses for 2017 & 2018
2017 Revenues 2017 Expenses 2018 Revenues 2018 Expenses
a. Enter the data in Microsoft Excel. Then, graph these data usin an Excel spreadsheet and the
graph tools. Import a copy of the graph from Excel into this Word document.
b. Discuss what you see on this graph
1. What specifically identifies trends in revenues and expenses?
a. From the line graph, I see that 2017 was a better year than 2018. You can see and
visualize the trend of how much money is made and spent. If the overall trend of a
line is on an upward slope, then it is favorable. The opposite is true for a downward
slope.
2. Interpret the information you see on the graph.
a. Discuss the pattern in revenues and expenses you would predict for 2019 based on
these data and explain your prediction.
i. To predict for 2019 based on the data from 2017 and 2018, it must first be
analyzed. From the data given from the table, it is noted from the line graph

8
COST MANAGEMENT
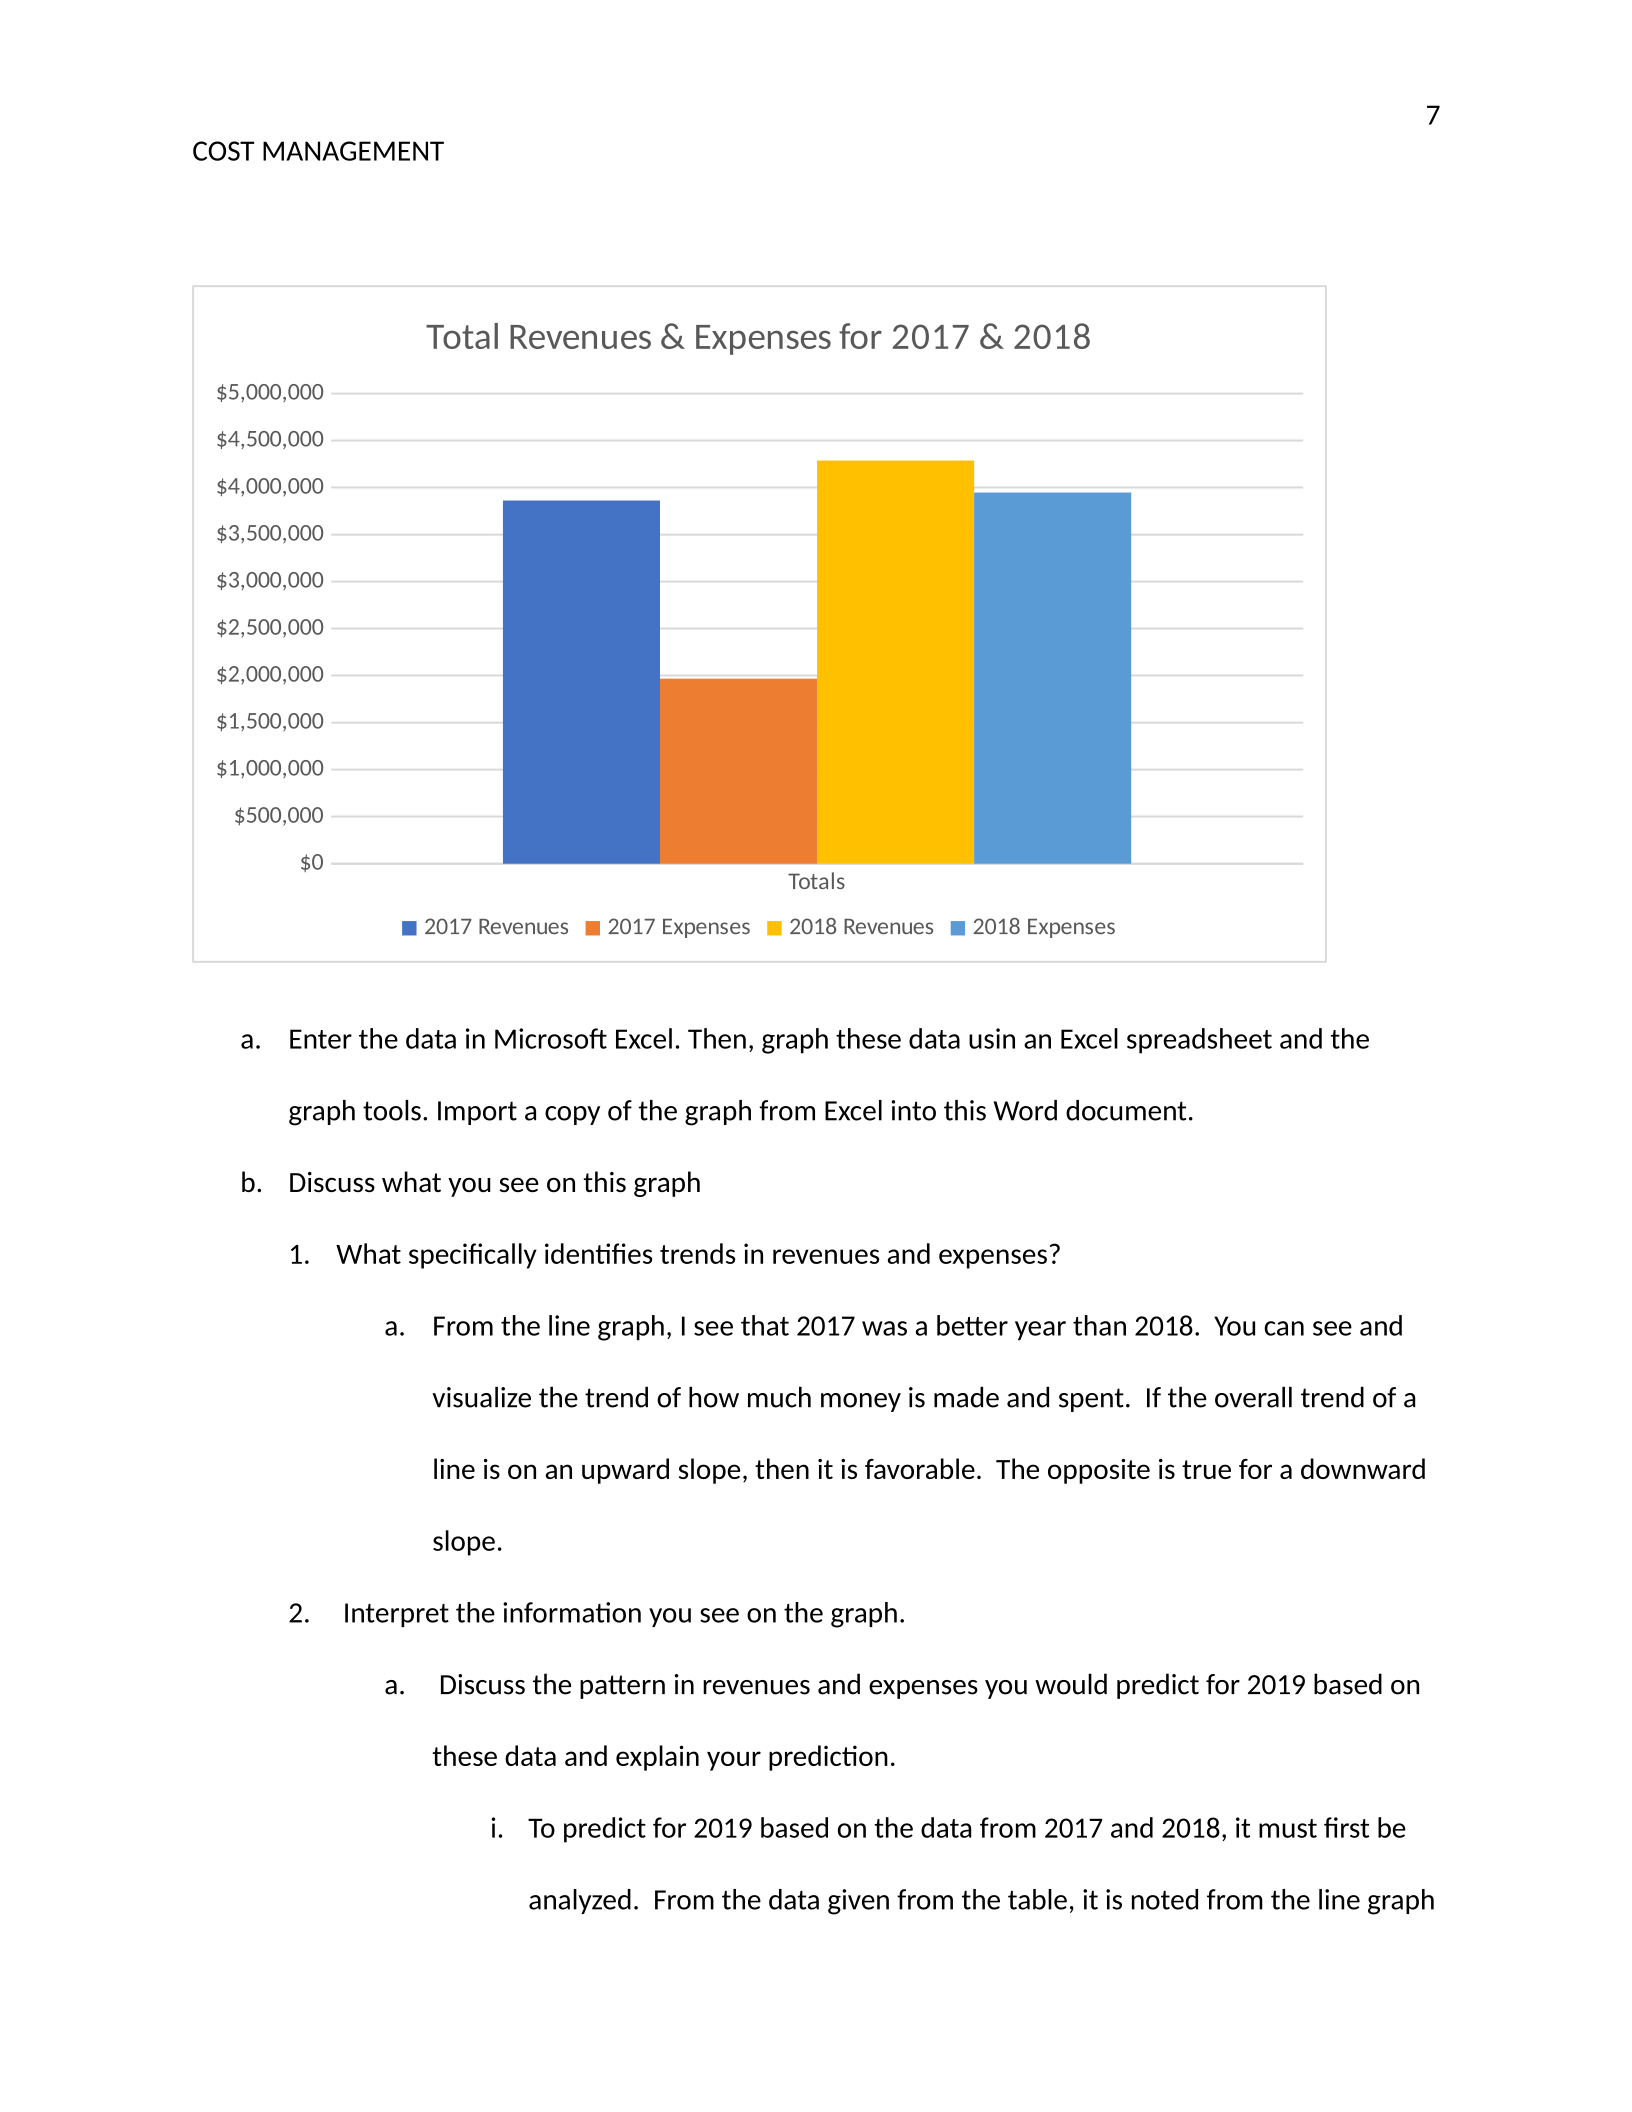
and the bar graph that shows that both years had almost had the same
revenues. However, there is a a big difference on the expenses between the
two years. One can see that the expenses for both years had a bigger jump
in expenses starting October. The expenses from 2018 had been higher
since the beginning of the year starting in January. Then in February 2018,
the expenses doubled from the previous year from 150K to 300K an
remained high the remainder of the year until there was another spike from
October to November, then decreased a bit by December. My prediction for
the 2019 trend, is that the revenues will mimic the same trend as the
previous two years and the expenses to be the average of the two years. I
would still expect a peak in expenses starting in October.
b. Discuss any actions the nurse manager should take based on these data for 2017
and 2018.
i. What worries me most is the huge increase in cost between the two years.
As seen in the bar graph of the total revenues and expenses for both years,
the expenses for 2018 almost doubled going from approximately $2 million
to approximately $4 million. This could be due from a variety of reasons
such as inflation over the year or there could have been a huge purchase or
investment made. As the nurse manager, I would dig deeper and request an
expense report sheet for 2018 to determine what purchases were made to
cause such a big increases in expenses for the year.

9
COST MANAGEMENT
References
Baluch , A. (2023). How Much Does Physical Therapy Cost? Forbes Health.
Ikeda, S., Shibanuma, A., Silwal, R., & Jimba, M. (2021). Factors associated with the length of stay at
health facilities after childbirth among mothers and newborns in Dhading, Nepal: a cross-sectional study.
BMJ Open, 11:e042058. https://doi.org/0.1136/bmjopen-2020-042058
Jones, C., Finkler, S., Kovner, C., & Mose, J. (2019). Financial management for nurse managers and
executives (5th ed.). Elsevier.
Simpson, K., Lyndon, A., Spetz, J., Gay, C. L., & Landstrom, G. L. (2019). Adherence to the awhonn staffing
guidelines as perceived by labor nurses. Nursing for Women's Health, 23(3), 217–223.
https://doi.org/10.1016/j.nwh.2019.03.003
Powered by TCPDF (www.tcpdf.org)

