



Learning Objectives- Chapter 15, Nursing Management: Patients With
Complications From Heart Disease
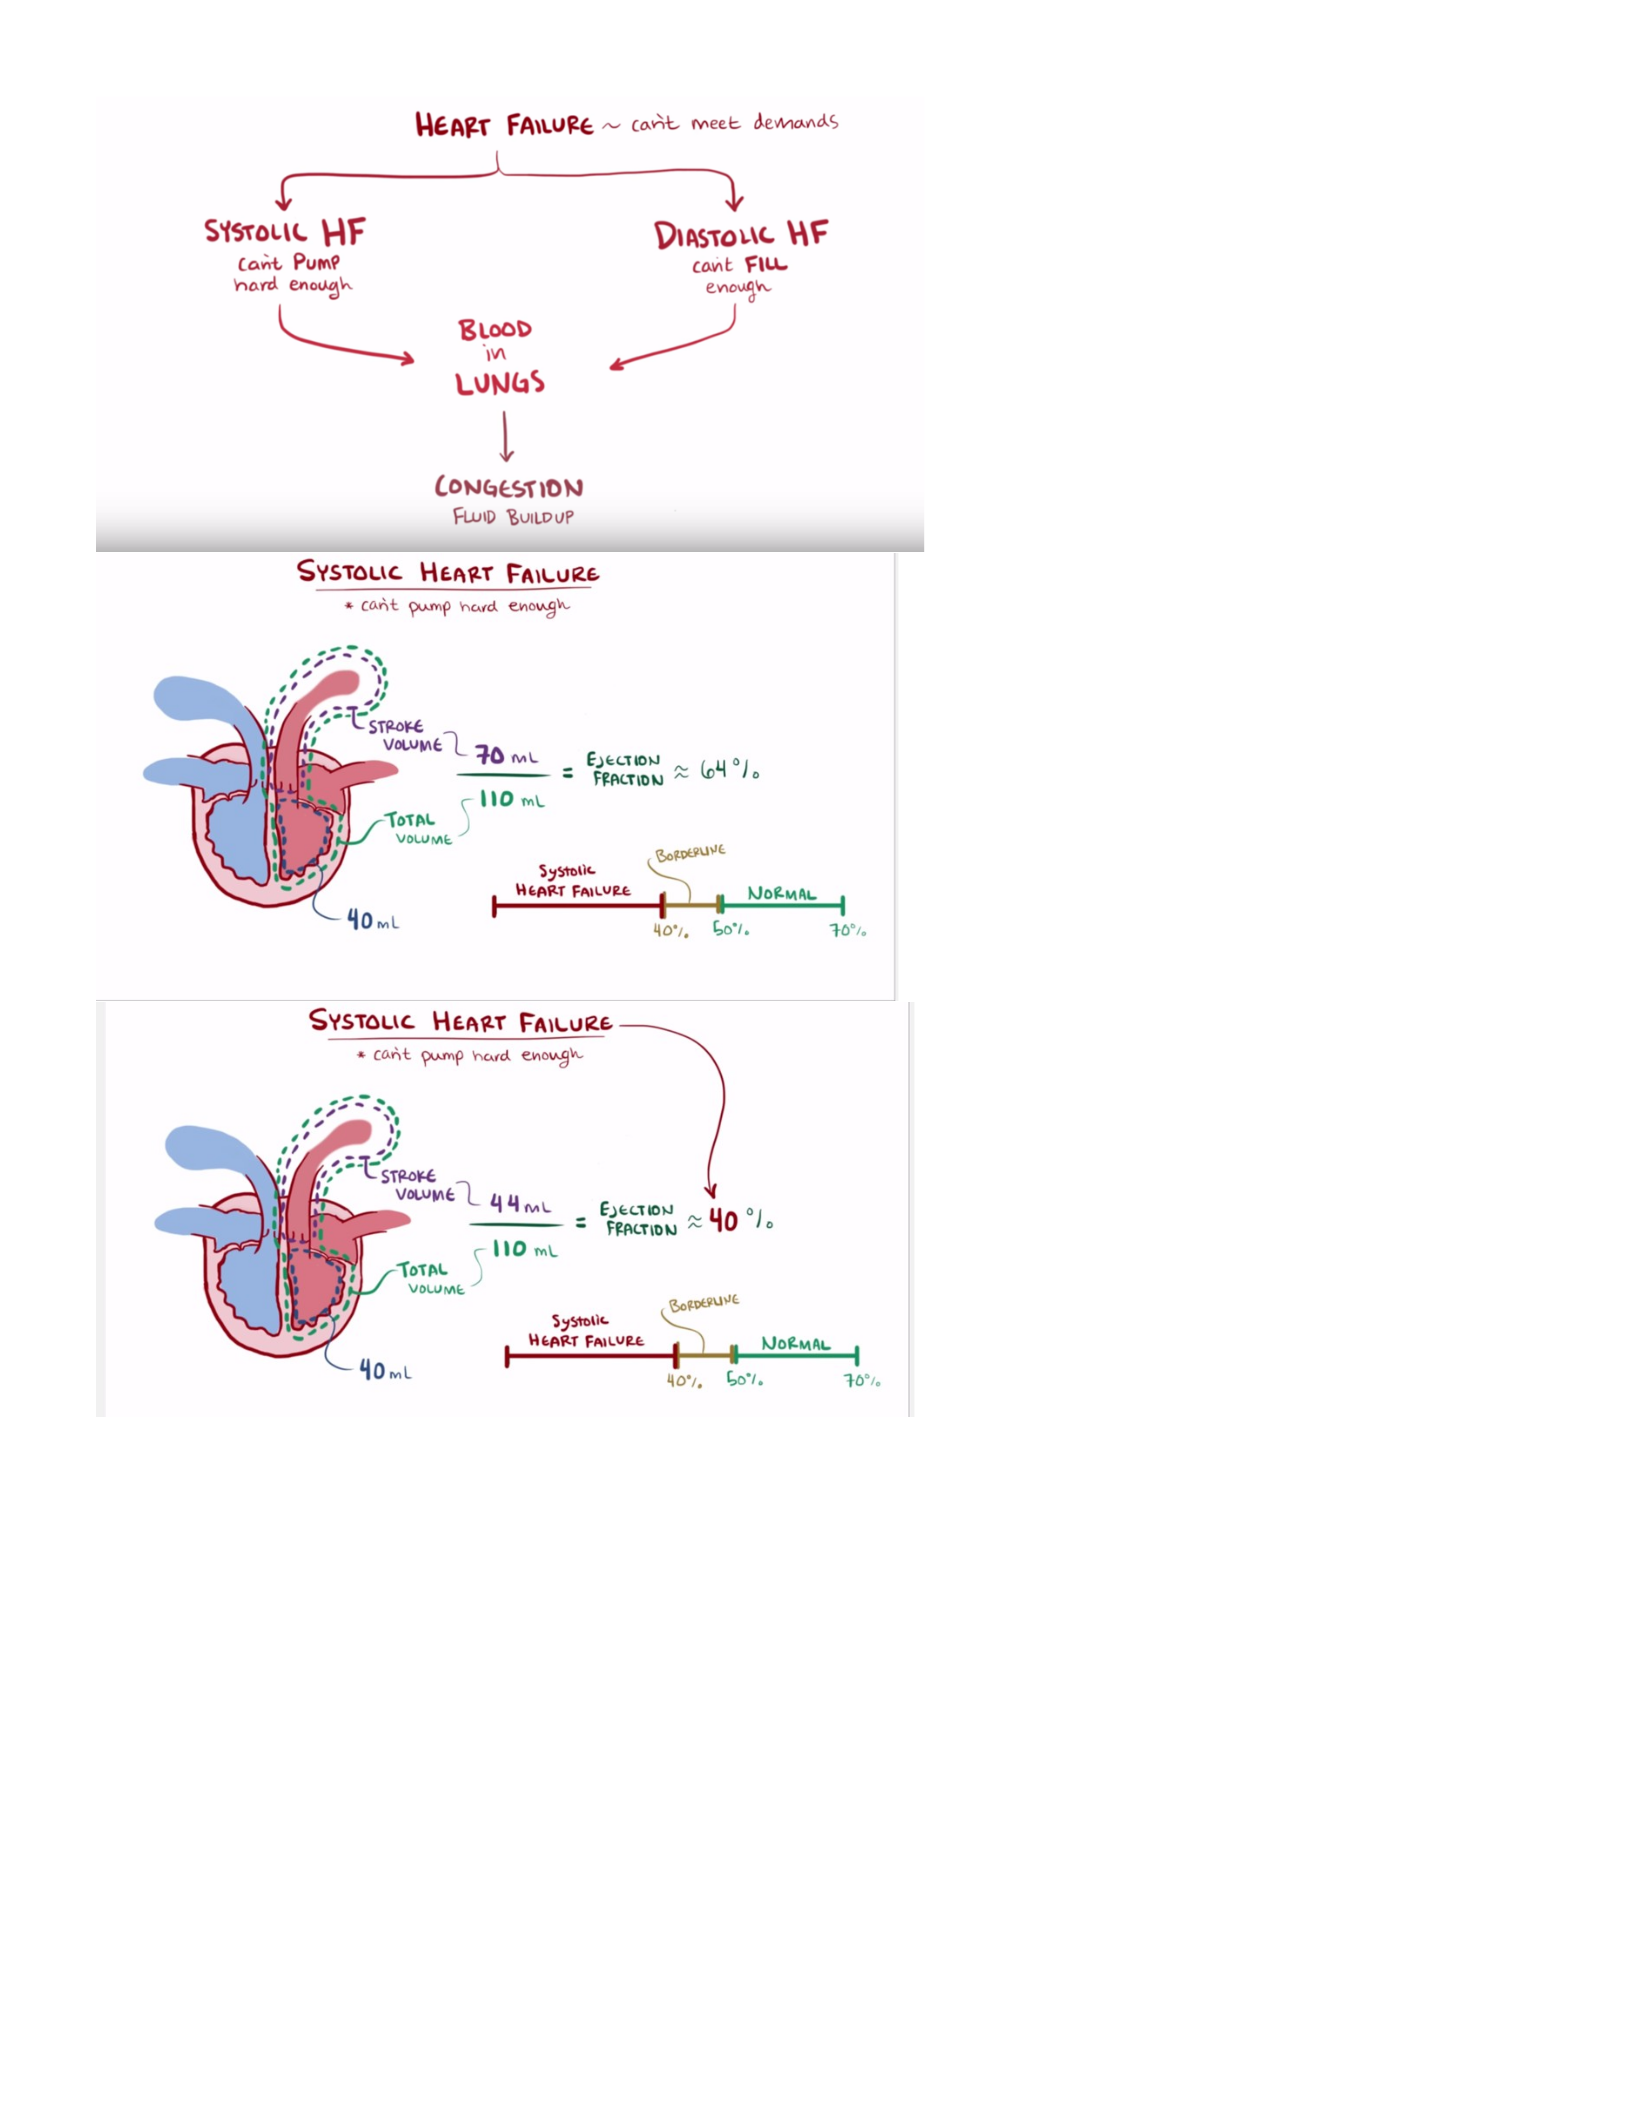
The term heart failure indicates there is a problem with contraction of the
heart (systole) or filling of the heart (diastole) that may or may not cause
pulmonary or peripheral congestion.
1. Describe risk factors and manifestations associated with systolic heart
failure (HF).
Inability of the heart to pump sufficient blood to meet the needs of the tissues for oxygen
and nutrients
Fluid overload or decreased tissue perfusion when the heart cannot generate a cardiac
output sufficient to meet body’s demands
Risk Factors
Major: >65y/o, males, hypertension, left ventricular hypertrophy, myocardial infarction,
valvular heart disease and obesity
Minor: Excessive alcohol consumption, smoking, high cholesterol, diabetes, toxins, sleep-
disordered breathing, chronic kidney disease, low socioeconomic status, psychological
stress, sedentary lifestyle and genetics
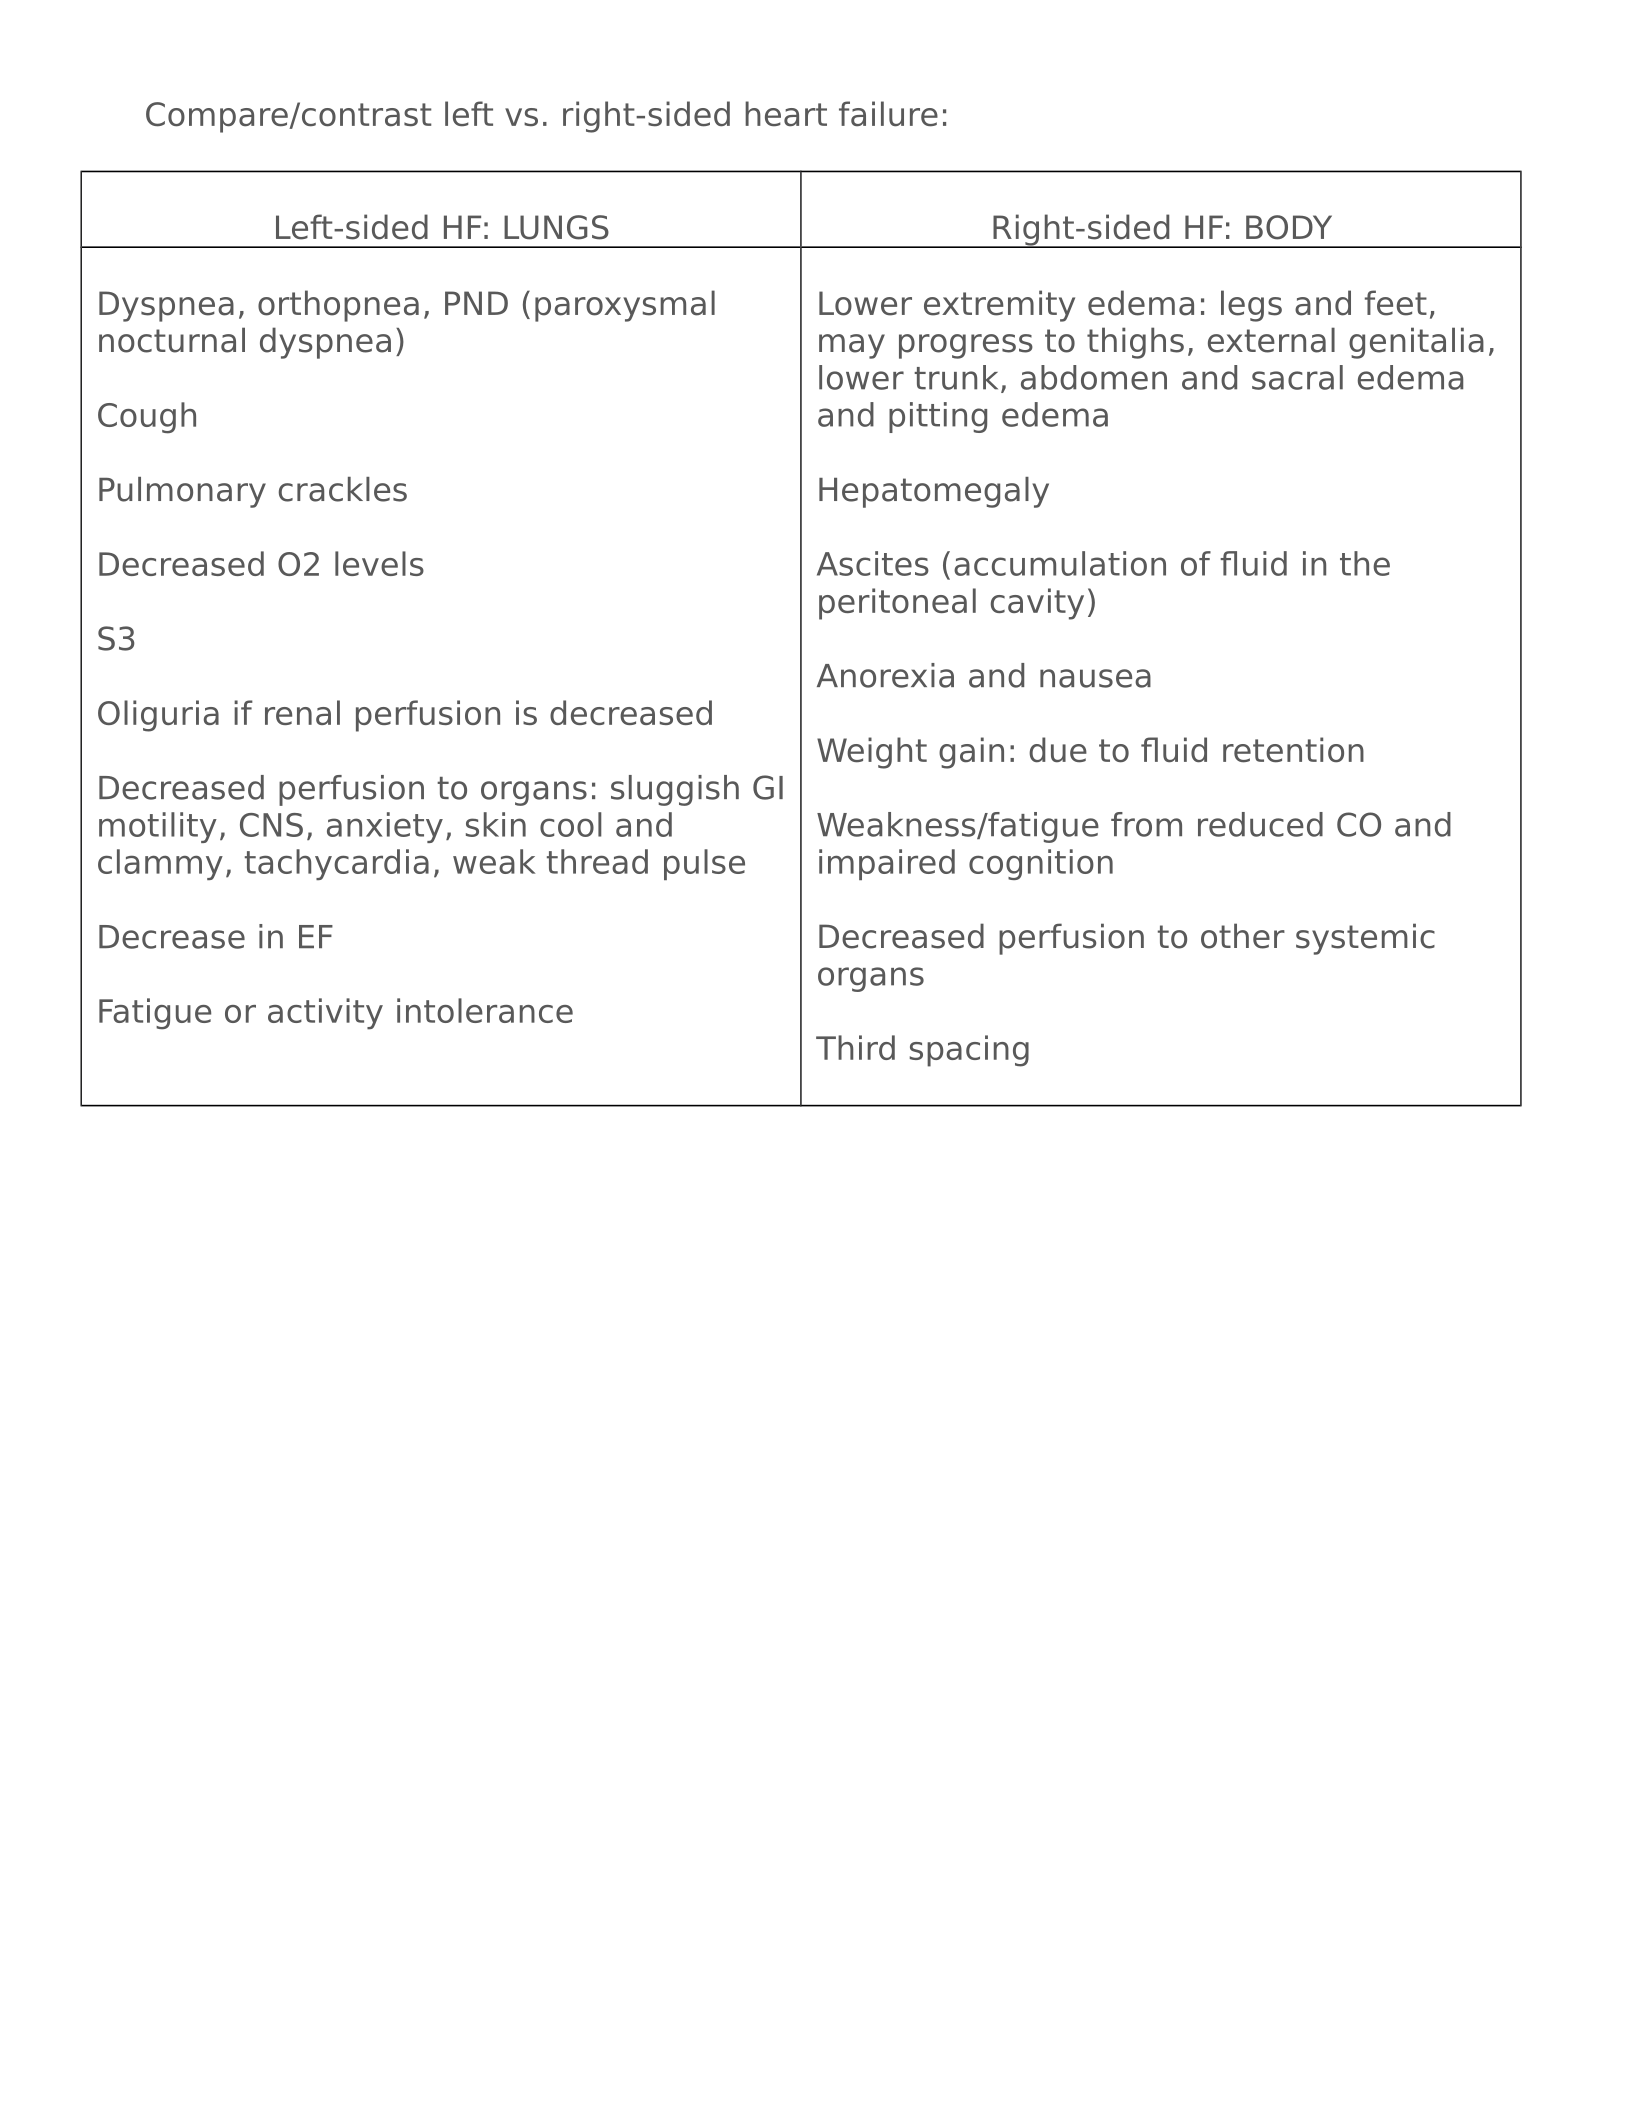
Compare/contrast left vs. right-sided heart failure:
Left-sided HF: LUNGS Right-sided HF: BODY
Dyspnea, orthopnea, PND (paroxysmal
nocturnal dyspnea)
Cough
Pulmonary crackles
Decreased O2 levels
S3
Oliguria if renal perfusion is decreased
Decreased perfusion to organs: sluggish GI
motility, CNS, anxiety, skin cool and
clammy, tachycardia, weak thread pulse
Decrease in EF
Fatigue or activity intolerance
Lower extremity edema: legs and feet,
may progress to thighs, external genitalia,
lower trunk, abdomen and sacral edema
and pitting edema
Hepatomegaly
Ascites (accumulation of fluid in the
peritoneal cavity)
Anorexia and nausea
Weight gain: due to fluid retention
Weakness/fatigue from reduced CO and
impaired cognition
Decreased perfusion to other systemic
organs
Third spacing
2. Describe the nursing management of patients with HF.
Assess s/s of pulmonary and systemic fluid overload are reported IMMEDIATELY. Monitor
pt’s I’s & O’s
Look forL SOB, cough, sleep disturbances, ask about number of pillows needed for sleep,
edema, abdominal symptoms, altered mental status, daily weight
What are the overall goals of management for the patient with heart failure?
Relieve s/s of HF
3. What does the nurse need to teach the patient with HF about:
Lifestyle changes: Restrict dietary sodium, avoid ETOH, NO SMOKING, weight
reduction when indicated and regular exercise. Recognize s/s to REPORT: weight gain,
increased SOB, fatigue and edema
Pharmacologic Therapy: ACE inhibitors, beta blockers, diuretics, digitalis
Diagnostics: Chest x-ray, ECG, echocardiogram,
Lab tests: CBC, electrolyte levels, BUN, creatinine, serum glucose, serum albumin, liver
function tests, TSH, urinalysis and BNP. High BNP indicate abnormal ventricular function
or symptomatic HF
4. Describe the assessment findings and management of patients with
pulmonary edema.
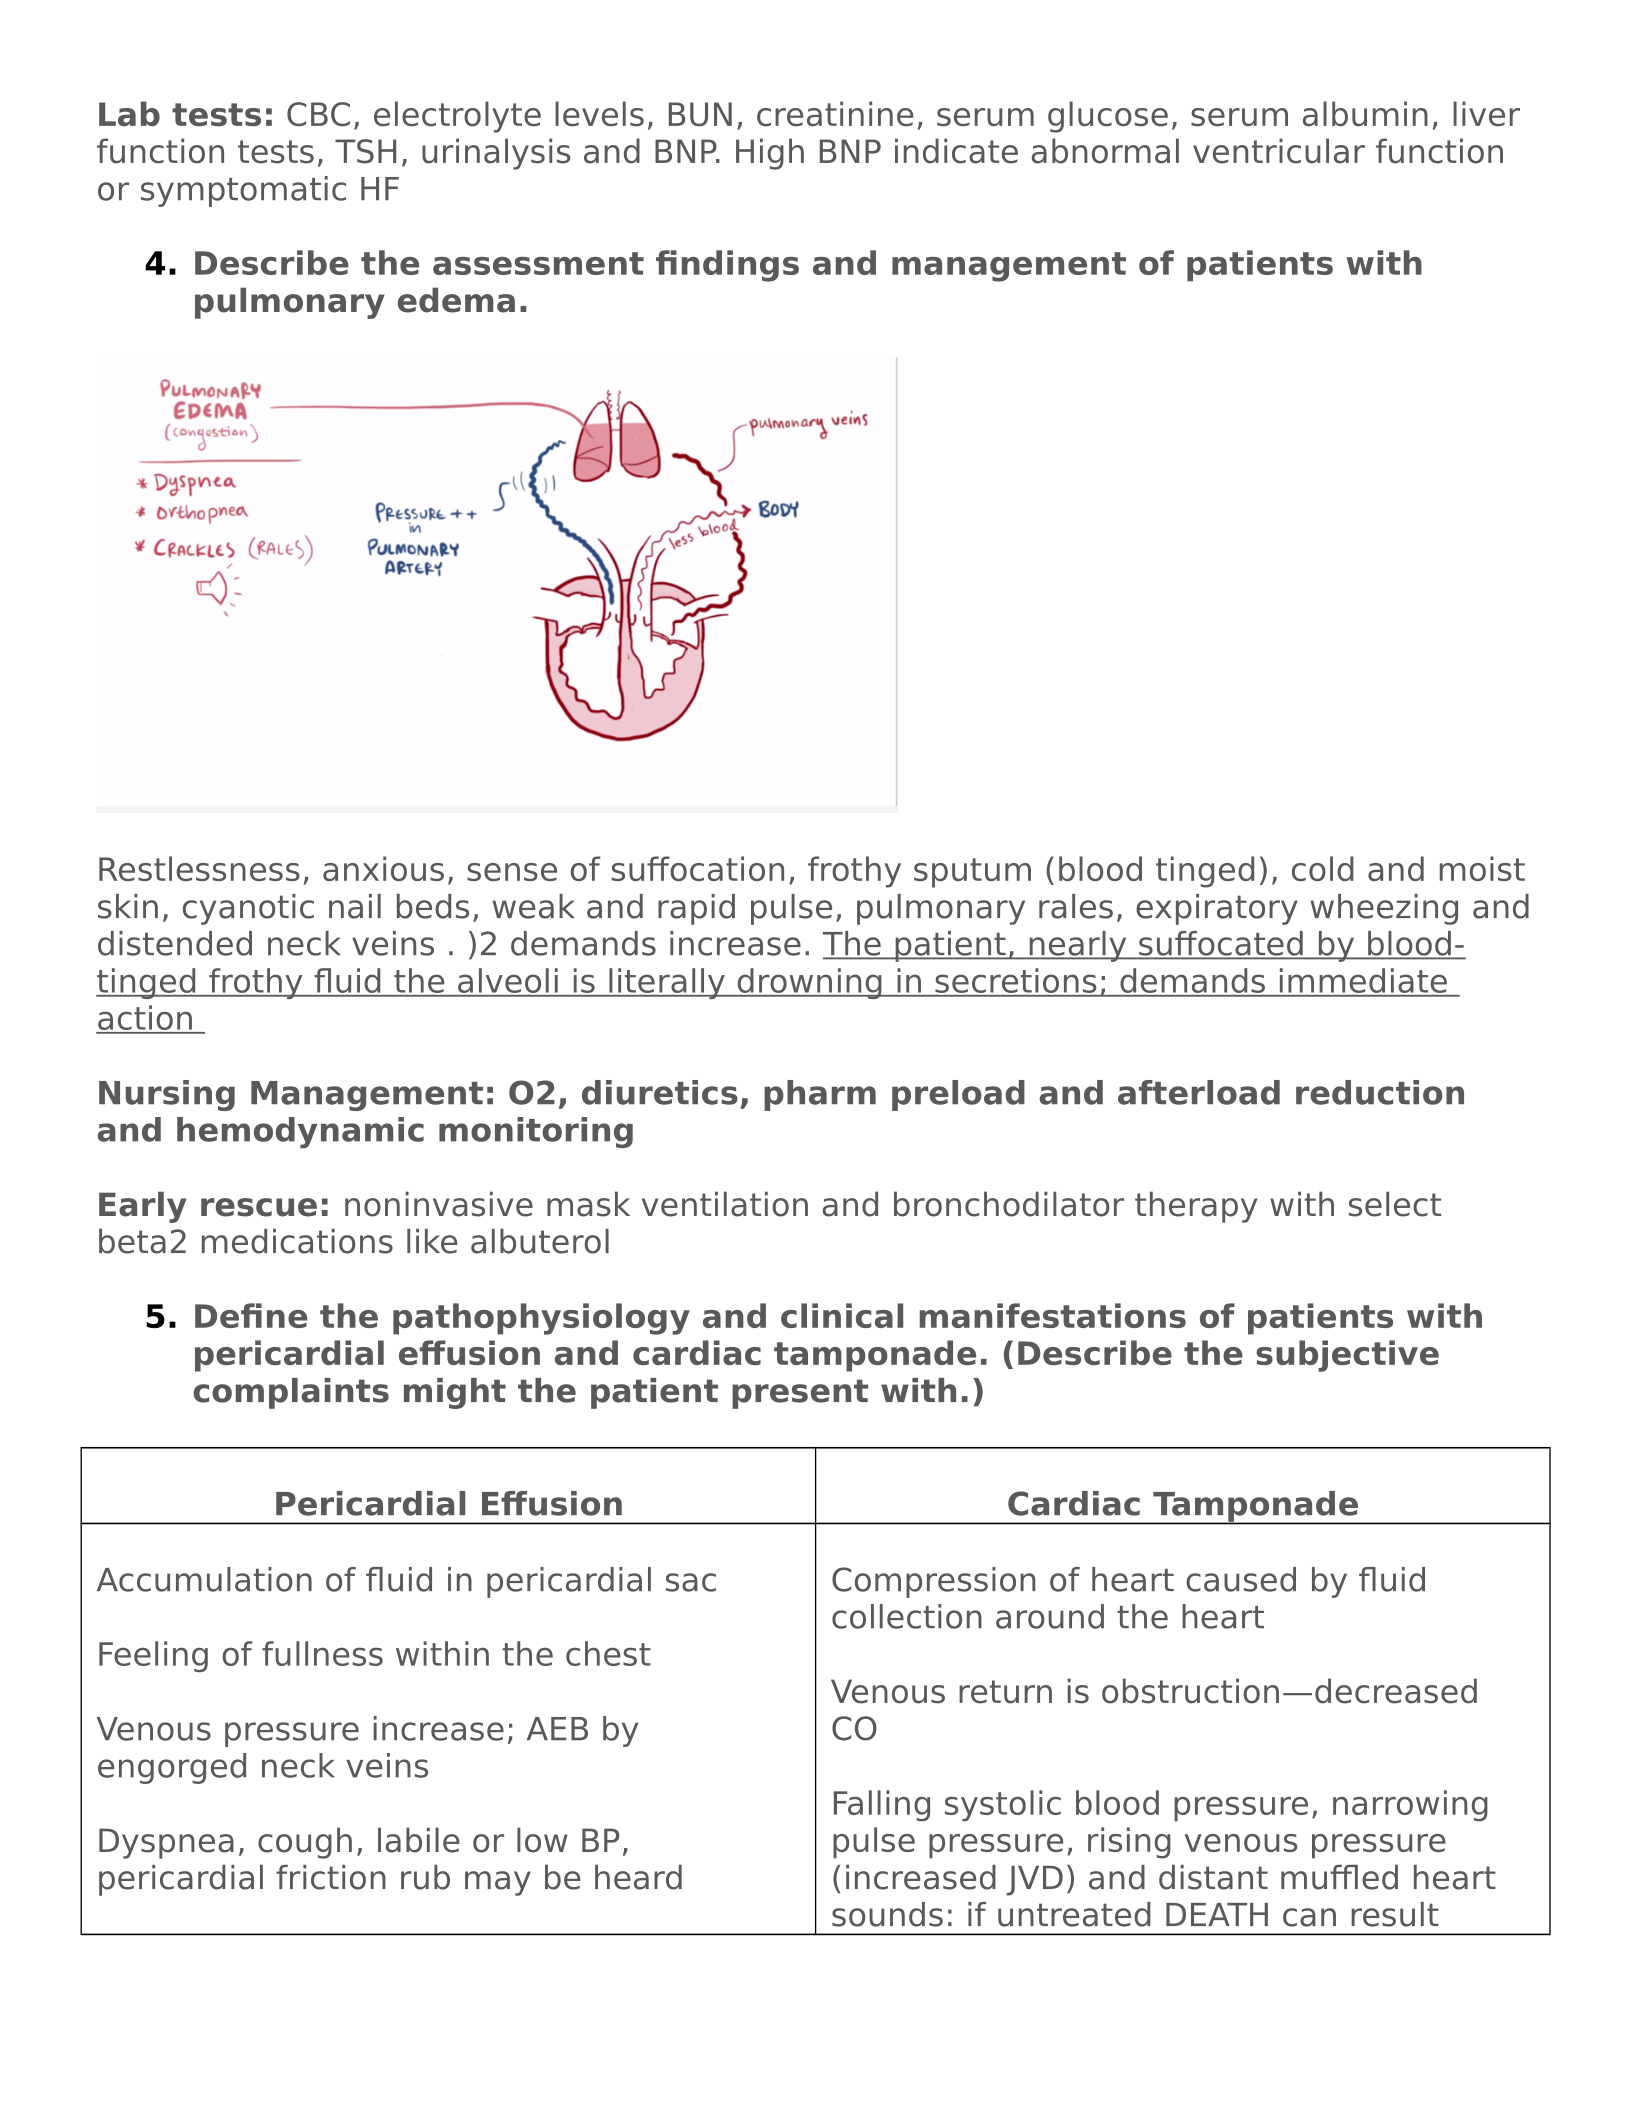
Restlessness, anxious, sense of suffocation, frothy sputum (blood tinged), cold and moist
skin, cyanotic nail beds, weak and rapid pulse, pulmonary rales, expiratory wheezing and
distended neck veins . )2 demands increase. The patient, nearly suffocated by blood-
tinged frothy fluid the alveoli is literally drowning in secretions; demands immediate
action
Nursing Management: O2, diuretics, pharm preload and afterload reduction
and hemodynamic monitoring
Early rescue: noninvasive mask ventilation and bronchodilator therapy with select
beta2 medications like albuterol
5. Define the pathophysiology and clinical manifestations of patients with
pericardial effusion and cardiac tamponade. (Describe the subjective
complaints might the patient present with.)
Pericardial Effusion Cardiac Tamponade
Accumulation of fluid in pericardial sac
Feeling of fullness within the chest
Venous pressure increase; AEB by
engorged neck veins
Dyspnea, cough, labile or low BP,
pericardial friction rub may be heard
Compression of heart caused by fluid
collection around the heart
Venous return is obstruction—decreased
CO
Falling systolic blood pressure, narrowing
pulse pressure, rising venous pressure
(increased JVD) and distant muffled heart
sounds: if untreated DEATH can result

How does pericardial effusion progress to cardiac tamponade?
When the pericardium is stretched to its maximum size: increased pericardial pressure,
venous return to the heart is obstructed and the amount of blood pumped out with each
contraction is reduced; decreasing CO
NOTE: Cardiogenic shock is a life-threatening condition with a high mortality
rate and will be managed in the ICU. Your job as a medical-surgical nurse is to
recognize the classic signs early in order to prevent organ failure.
Shock is caused by decreased CO and vital organs SHUT DOWN
Decreased BP, increased HR, cyanosis, N/V, clammy skin, restlessness
6. Describe the emergency management of patients with cardiac arrest
A: MAINTAIN OPEN AIRWAY
List three possible causes of cardiac arrest:
1. Cardiac electrical event (v-fib)
2. Bradycardia-progressive, profound
3. No heart rhythm
What is the difference between cardiac arrest and myocardial infarction?
Cardiac Arrest: heart ceases to produce effective pulse and circulate blood:
consciousness, pulse and BPLOST immediately
MI: death to heart tissue
What is PEA?
PULSELESS ELECTRICAL ACTIVITY
Electrical activity is present but there is ineffective cardiac contraction or circulating
volume. Can be caused by hypovolemia, hypoxia, hypothermia, hyperkalemia, massive
PE, MI and medication overdose
How is cardiac arrest treated?
Powered by TCPDF (www.tcpdf.org)

