



MALARIA IN PREGNANCY

•
Malaria is more common in pregnancy compared to the
general population.
•
The non- immune, primigravidae are usually the most
affected(prevalence & complications)
•
The increased risk of contracting malaria may be due to
•
Decreased immunity
•
Hormonal changes
•
Higher attractiveness to mosquitos
•
The physiological changes of pregnancy and the pathological
changes due to malaria have a synergistic effect on the course
of each other
•
Thus making the life difficult for the mother, the child and the
treating physician.

In pregnancy, malaria tends to be more atypical in presentation.
This could be due to the hormonal, immunological and
hematological changes of pregnancy
In Kenya, the effects of malaria on pregnancy outcomes were
measured among 912 women who delivered in Kilifi district
hospital (Shulman et al., 2001).
The authors performed placental histology to assess the
prevalence of active or past malaria and its association with
anemia and LBW.
They found a high prevalence of active or past malaria in all
gravidities, ranging from 64% in primigravidae to 30% in
gravidities 5 and above. In gravidities 1-4, active malaria
infection was associated with severe maternal anemia, adjusted
OR 2.21 (95% Cl, 1.36-3.61).

TRANSMISSION
Predominantly via bite of infected female anopheles sp mosquito
Congenital
Blood transfusions
Organ transplant
Sharing contaminated needles

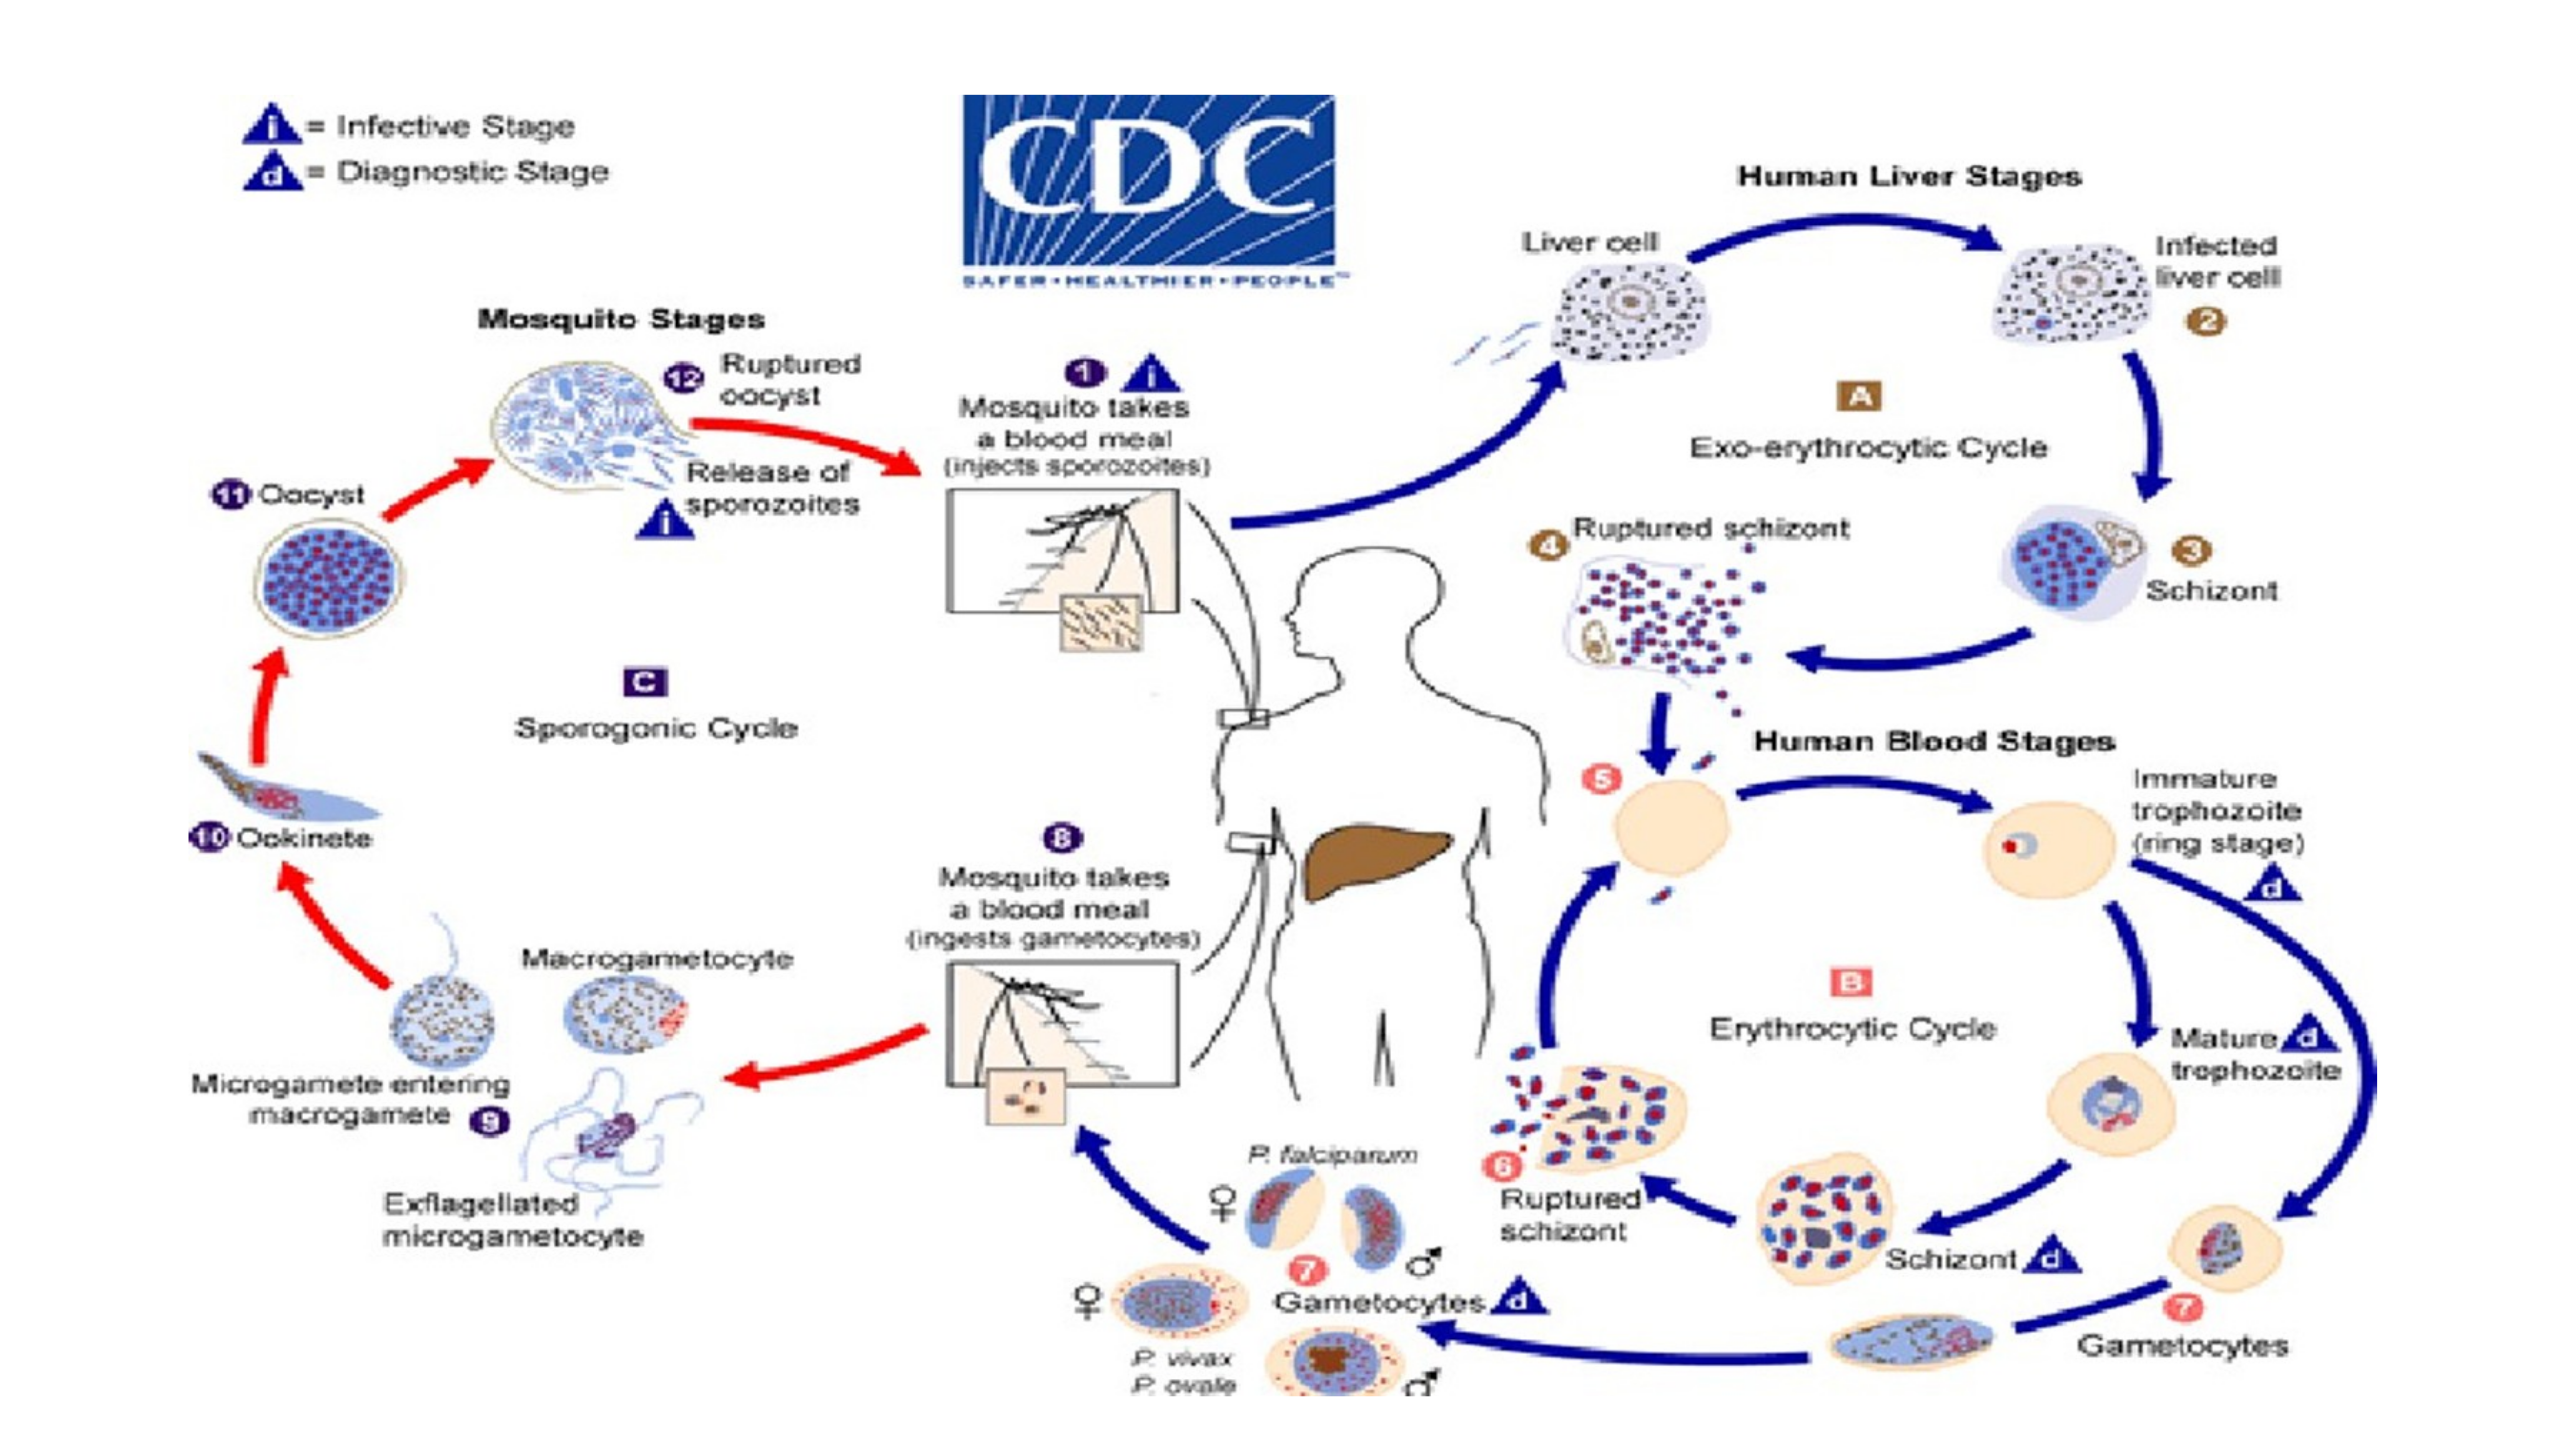
Pathogenesis of malaria
Starts by injection of Plasmodium sporozoites via a bite from an infected mosquito
In the Exoerythrocytic Stage, usually asymptomatic, Sporozoites are injected during
blood meal.
Sporozoites travel to liver, bind using Circumsporozoite (CS) protein. Multiply many
thousand fold to produce mature tissue schizonts containing thousands (10 – 30
thousand) merozoites.
In 6 – 16 days hepatocytes rupture releasing merozoites into bloodstream where they
interact with specific RBC membrane proteins and invade them to start erythrocytic
stage.
P vivax and ovale form hypnozoites that are schizonts that can remain dormant for
months to years.

In Erythrocytic Stage;
•Merozoites undergo asexual cycle maturing from ring forms to
trophozoites to mature red cell schizonts over 48 hours (falciparum,
vivax, ovale) & 72 hours (malariae).
•The merozoites rupture out of the red cell and can then repeat cycle
by infecting new red cells
•Some merozoites develop into non multiplying sexual forms-
gametocytes. These gametocytes are crucial in for perpetuating the
life cycle as they are ingested by a feeding mosquito and undergo
sexual reproduction within the mosquito midgut: a zygote matures to
ookinete then sporozoites that migrate to mosquito salivary glands
and can be inoculated at the next blood meal.

At the completion of the schizogony within the red cells, (48hrs for
P. falciparum) newly developed merozoites are released by the
lysis of infected erythrocytes
Along with them, numerous waste substances are also released
into the blood.
These include red cell membrane products, hemozoin pigment,
and other toxic factors such as glycosylphosphatidylinositol (GPI)

These products, particularly the GPI, activate macrophages and
endothelial cells to secrete cytokines and inflammatory mediators
such as TNF-alpha, IFN-Y, Il-I, IL-6, IL-8, MCSF, and lymphotoxin, as
well as superoxide and nitric oxide (NO).
The systemic manifestations of malaria have been largely
attributed to these cytokines
d=
infective
Stage
Ad®=
Ciagnostic
Stage
Mosquito
Stages
es
a
geet
lps.
\*
ee
SESS
‘
Sporogenic
Cycle
{
e
;
Human
Blood
Stages
a
a
=,
Immature
a
'
—
trophazoite
woraurorscs
TP
nw
SA
a
blood
meal
-
—
wecrapened
(ingests
gareqocytes)
&
&
o
ge
_—
—
|
ad
Erythrocytic
Cycle
Mature
de
Micregamete
entenng
sl
+
‘te
es
G
mae
2
=
Bats
@
fadopanen
-
a”
—
"
Exflageliated
oe
)
>
Ruptured
Ray
eee
asa
ae
microgametocyte
e
sc
seman
Pe?
schizonde
|
Ga
.

Pathogenetic Characteristics of Severe Malaria
1) Cytoadherence
2) Sequestration
3) Rosetting

Placental Malaria
• Caused by P. falciparum—infected erythrocytes that bind to
placental tissue.
• Binding is mediated by VAR2CSA, a parasite antigen which interacts
with chondroitin sulfate A (CSA) on the syncytiotrophoblast
• The VAR2CSA is coded by the var2csa gene. By this process, the
parasites avoid being filtered through the spleen
• Also it impairs movements of nutrients across the placenta

Cont.
•Consequences include maternal anemia and fetal growth
retardation. Antibodies against VAR2CSA occur during pregnancy
after exposure to infected erythrocytes sequestering in the placenta
•Concentrations of these antibodies increase with parity
• Placental changes in malaria infection are also due to hemozoin
deposition & increased monocyte deposition

Clinical presentation
•Fever
•Headache
•Joint pains
• Malaise
•Nausea +/-vomiting, +/- diarrhea
•Abdominal pain Poor appetite
• Pallor
•Splenomegaly

EFFECT OF MALARIA ON FOETUS
•
Malaria in pregnancy is detrimental to foetus due to;
a. high grade fever
b. placental insufficiency
c. hypoglycemia
d. Anemia
•
N/B: primigravida develop more clinical symptoms of malaria,
women with higher immunity may not demonstrate symptoms, but they
may have more placental burden so more fetal complications

•Result in;
i. Spontaneous abortion
ii. Premature birth
iii. Still birth
iv. Low birth weight
v. Congenital malaria <5% (b/c of protection by maternal IgG) more
with plasmodium malariae
vi. Perinatal and neonatal mortality

Poor prognosis parameter
•Parasitemia >5%
•Packed cell volume <30%
•Hemoglobin <7.1 gm%
•Hypoglycemia blood glucose <40 mg%

Complications to the mother
i. Anemia
ii. Abortion and its complications
iii. Premature labour
iv. Cerebral malaria
v. AKI
vi. Pulmonary edema

Complications to the fetus
•IUGR
•Congenital infection
Complications to the newborn
•Premature delivery
•Low birth weight and its complications
•Congenital/neonatal malaria

Management

Investigations
•Antigen detection techniques : - MRDT-2/pLDH(PfPAN))
•Peripheral blood smear
•PCR based assay
•Antibody test
•Placental blood
•Others depending on the clinical presentation

Treatment of malaria in pregnancy
Depends on
Severity
Gestational age

Supportive treatment
• Treatment of anemia (BT, FA)
• Correction of electrolyte imbalance
• Oxygen + Diuretics in pulmonary oedema
• Dialysis for ARF
• Anticonvulsants
• ICU care for CM
• Monitoring of the fetal growth & health

A. Uncomplicated malaria
In the first trimester,
•
Pregnant women with uncomplicated malaria should
be treated with quinine tablets for seven days
•
The dose is 10 mg/kg every 8 hours for 7days
•
Do not exceed a maximum dose of 600mg per day

In the second and third trimester
•Artemether-Lumefantrine should be used as medicine of choice
•The dose is 4 tabs stat then 8hours after the first dose then 12hourIy for
2days (a total of three days)
•Alternatively;
•Dihydoartemisinin-Piperaquine (DPQ)
•Artesunate-Amodiaquine
Cont.

B. Severe malaria
The primary objective of treatment in severe malaria is to prevent death.
The secondary objective is to prevent disabilities and to prevent
recrudescent infection.
In the first trimester
The medicine of choice for treatment of severe malaria in the first
trimester is IV Quinine(dose)
In the second and third trimester
The medicine of choice for treatment of severe malaria in 2nd and 3rd
trimester of pregnancy is Inj. Artesunate

•The dose is 2.4 mg/kg given at time 0 hour, then at 12 hours and 24 hours
Followed by A-Lu for 3days
• The first oral dose should start 8hrs after the last injection
•Quinine should be used only if Artesunate injectable is not available

Treatment
According to WHO recommendation,
• Treatment of severe malaria is with Inj Artesunate for both children
and adults including infants, pregnant women in all trimesters and
lactating women.
•Inj Artesunate should be given for at least 24hrs and until patient can
tolerate oral medication, then they should complete treatment with
3days of ACT
• If Artesunate is unavailable, Inj Artemether (1M) should be given
• If Artemether is unavailable, Inj Quinine should be given

Prevention
Available options are:
•Vector control
•Insecticide Treated Nets (IT NS)
•Residual house hold spraying
•Environmental management
•Drug prophylaxis
•Intermittent preventive treatment (IPTp)
•Alternative- DPQ (not yet adopted)
•Vaccine??

Intermittent preventive treatment (IPTp)
•The drug of choice for IPTp is Sulfadoxine/Pyrimethamine (SP)
•Reduces the risk of Placental malaria, Low birth weight and Maternal
illness
•Dosing should start as early as possible in the second trimester
•Should be given at least 1 month apart, at least 3 doses
•SP can be administered up to the time of delivery

Intermittent preventive
treatment (IPTp) cont..
•IPTp-SP prevents adverse maternal and fetal outcomes
from malaria, including placental infection, clinical
malaria, maternal anemia, low birth weight, and
neonatal mortality. It's cost-effective and provides
significant benefits despite SP resistance, reducing
neonatal mortality and low birth weight.

Chemoprophylaxis during pregnancy
Malaria being potentially fatal to both the mother and the foetus, this should
be an important part of antenatal care in areas of high transmission.
— All pregnant women, who remain in the malarial endemic area :during
their pregnancy, should be protected with chemoprophylaxis
Choice of anti malarials for chemo prophylaxis
— Chloroquine being the safest drug in pregnancy, should be the first choice
— In areas with known resistance to Chloroquine
Pyrimethamine + Sulpha, Mefloquine or Proguanil can be used.
But these drugs should be started only after 1st trimester.

Doses for chemoprophylaxis
•Chloroquine: - 300mg base, administered once every week.
•Pyrimethamine-25mg + Sulphadoxine-500mg: One tablet once
weekly.
•Mefloquine: -250mg weekly— Dose may have to be increased in the
last trimester, in view of the accelerated clearance of the drug.
•Proguanil: - 150-200mg / day.
note; Doxycycline and primaquine are not recommended during
pregnancy as they may harm your unborn baby.

THANK YOU

