


Review classmates' threads carefully noting anything of which you had a
different understanding. Add any point(s) you feel are important that might be
missing.
After reading your classmates' opinions, state if and why you agree or
disagree. Support your assertions with evidence from the Bible, text, and
articles, using AMA citations. Integrate findings from articles that may add a
different perspective than your classmates' perspectives.
1. DISCUSSION POST
2. For me personally, this topic is where God and science collide. Many
scientists would argue that genes represent the most immutable
determinates of ourselves, they set limits to what we are capable of
being and doing and provide us with our potential in life.1 I understand
that science does support this but as a Christian, I find this statement
untrue because with God there are no limits to what we are capable of.
In addition, in the Bible, God constantly speaks about promises,
blessings, and curses which are passed on from generation to
generation. For example, the lineage of Abraham, Isaac, Ishmael, and
David. Lineage in the Bible is basically genetics; blessings and curses
translate into genetics as health and diseases. This is why we see
diseases passed from generation to generation and scientists would
say they are genetically predisposed to something. However, God sent
Jesus for our sins and to heal us from sickness and disease. In 2
Corinthians 5:17 it says, “If anyone is in Christ, he is a new creation.
The old has passed away; behold, the new has come”2. Jesus
changes everything, for those who believe in Jesus they are a new
creation, sickness, disease, and generational curses are wiped away
and we are new creations. People are not doomed to the fate of their
genetics.
As nutrition and dietetics professionals the first thing we need to do is pray.
We understand the science behind our bodies, health, and nutrition but
ultimately, we need to put our trust in God and not science. We can recognize
these generational curses such as diabetes, obesity, and cancer and help
guide our patients on a path of nutritional health and break these generational
curses, in the name of Jesus.
The role of a nutrition professional is to determine the problem or health goal
and advise a diet that will support the desired outcome the patient or health
professional is seeking. The nutrition professional needs to be prepared with
the necessary knowledge and skills to treat the patient with solid evidence-
based dietetics and nutrition practices and take into consideration nutritional
genomics to make a more tailored approach to diet.3 Nutrigenomics is the
scientific study of the way particular genes and bioactive food components
interact. This helps provide professionals with a basis for understanding the
health consequences of eating behaviors which may be different for each
person. Nutrition professionals understand that dietary components can
influence or change the risk of disease development by modulating the
processes involved with onset, incidence, progression, and severity. The food

prescribed can act on the human genome directly or indirectly altering the
expression of genes and gene products. Nutrition professionals can create a
diet for an individual to potentially compensate for genetic polymorphisms.
The outcome of the diet is dependent on the balance of health and disease
states and on an individual’s genetic background1.
Based on up-to-date knowledge of the relationship between diet and disease
the guidelines do not take into consideration the account of genetics and
epigenetic variations and how the variations can play a role in an individual
response to dietary factors such as health and disease. Genomics offers more
insight into a patient’s genetic disposition, and I think modifications can be
made to prevent diabetes, obesity, and cancer. There is not a blanket solution
for dietary and nutritional health. Each patient will need a personalized
nutrition plan taking into consideration current health status, food preferences,
environmental factors, and if available, genotype.3 God created our bodies so
unique, it is important that a professional remember that each person has a
different genetic background so a different dietary intervention will be needed
for each person. 4 Yes, gene-environment interactions are relevant to public
health nutrition because people may be presumed genetically more
susceptible to a disease so a diet prescription can be tapered to meet those
needs. However, environmental interactions can alter the onset of a disease
or increase the onset of disease. 1
Reference
Trujillo E, Davis C, Milner J. Nutrigenomics, proteomics, metabolomics, and
the practice of dietetics. Journal of the American Dietetic Association.
2006;106(3):403-413. doi:https://doi.org/10.1016/j.jada.2005.12.002
English Standard Version Bible. Crossway Bibles, Good News Publishers;
2016. https://esv.literalword.com
Nelms, MN, Sucher, KP. Nutrition Therapy and Pathophysiology. 4th ed.
Cengage; 2019.
Gene–environment interactions and public health nutrition. Public Health
Nutrition. 2006;9(7):821-822. doi:https://doi.org/10.1017/phn20062001

Editorial
Gene–environment interactions and public health nutrition
A non-scientific survey of the scientific literature reveals
that the number of articles dealing with gene–environ-
ment interactions has exploded over the past decade. A
Medline search on the terms ‘gene’, ‘environment’ and
‘interaction’ shows 120 articles published in 1995, 309 in
2000 and 1211 in 2005. In this issue of Public Health
Nutrition, two articles join that surge, in some sense
marking a shift in the articles we are seeing and publishing
in our journal.
Using data from the Swedish Young Male Twins Register,
Karnehed et al.
1
found that low physical activity and low
fibre intake were significantly associated with greater waist
circumference in their sample. Moreover, they discovered
an interaction between genetic susceptibility and physical
activity: among twins with higher genetic susceptibility to
greater waist circumference, low physical activity appeared
to have a greater effect on attained waist circumference
than it did among twins at low genetic risk.
In the second of the two articles, Salminen et al.
2
examined data from a 2- to 3-year family-based health
education and counselling intervention. They saw no
significant differences in serum lipids between risk
(children with 13/4 or 14/4 genotype) and non-risk
(children with 12/3 or 13/3 genotype) groups, with the
exception of the total cholesterol/high-density lipoprotein
cholesterol ratio among boys. Their findings indicate that
the effects of the intervention were similar in children
regardless of their apolipoprotein E genotype.
The two articles raise two methodological issues of
concern in gene–environment (G £E) studies: the
measurement of genetic factors and the measurement of
environmental (or more broadly, non-genetic) factors.
Error in the measurement of non-genetic factors is a
longstanding problem in epidemiology and is no less a
concern in epidemiological studies on G £E interactions.
Karnehed et al. discuss the possible implications of error
in measuring dietary intake and physical activity in their
observational study of male twins. But even in an
intervention study, in which we have the greatest control
over the ‘exposure’ of interest, we can raise questions
about the exposure that was measured. Would a more
intensive intervention have had a more visible effect?
Might we have seen different results if the intervention had
targeted a more specific age group (e.g. 6–9-year-olds)? In
any case, the interpretation of findings for non-genetic
factors merits close scrutiny, as it always does.
The measurement of genetic characteristics, likewise,
merits close scrutiny. A twin study allows for a clever and
efficient analysis, but classifying twins as being at high or
low genetic risk based on their concordance in falling
above or below the residual median for waist circumfer-
ence leaves some room for interpretation. To what extent
does their concordance reflect similar early-life environ-
ment rather than true genetic risk? That the G £E analysis
findings for dizygotic twins resembled those for mono-
zygotic twins, in fact, gives some support to the possibility
that shared environment contributed to their concordant
risk status. Salminen et al. use a different approach to
represent the ‘gene’ in their G £E study by selecting a
polymorphism hypothesised a priori to affect cholesterol
absorption and plasma lipids. The question that it leaves
unanswered, though certainly not by any shortcoming of
the study’s design, is whether we might expect to find any
genes by which responders to such an intervention can be
distinguished from non-responders.
A final question that we might ask as readers of Public
Health Nutrition is this: are articles on G £E interactions
relevant to public health nutrition? A purist might argue
that the greatest value of G £E studies is in their potential
to elucidate aetiology and to suggest more targeted
recommendations and interventions – but public health
nutritionists are more concerned with practical impli-
cations than with aetiology, with broad population
measures rather than with specific, targeted advice.
I would argue that G £E articles are relevant to the field
of public health nutrition, and hence to our journal, in
three ways. First, the studies generally reaffirm the
importance of the environment in G £E studies. Less
physical activity, for example, predicted greater waist
circumference among male twins regardless of their
presumed genetic susceptibility
1
. By itself, confirming the
importance of non-genetic factors is of course not reason
enough for an article to be published in Public Health
Nutrition. But a corollary is that G £E articles in Public
Health Nutrition must have a relevant E component and
so, in that sense, they retain their broader relevance.
A second reason that G £E articles are relevant is that
they provide some sense as to the limits of public health
measures. Besides pointing out how unfair genetic
inheritance can be – in the study by Karnehed et al., for
example, ‘45 minutes of moderate PA may be enough to
prevent weight gain in some, whereas 60 minutes might be
too little in others’ – G £E studies also reveal whether
variability in genetic characteristics contributes to varia-
bility in the success or failure of public health measures
and recommendations.
qThe Author 2006
Public Health Nutrition: 9(7), 821–822 DOI: 10.1017/PHN20062001
https://doi.org/10.1017/PHN20062001 Published online by Cambridge University Press

Finally, besides the academic reasons generally given
for interest in G £E studies – aetiological knowledge,
targeted prevention, etc. – there is the desire for
knowledge of self. Gene therapy notwithstanding,
genes represent the most immutable determinants of
ourselves. They set limits on what we are capable of
being and doing, and they provide us with our
potential in life. G £E studies often and necessarily
appear to dwell in the minutiae of biology, in response
to which we might wonder if we are being reduced to
a single gene or protein. But each study is part of an
endeavour to determine the extent to which we are
able to maintain our own health and, in the bigger
picture, to control our own destinies. Studies at the
interface of nutrition and genetics can be worrisome
when they appear too far-flung from the realm of
public health. Still, such studies inform us about our
potential and our limits as public health practitioners
(and as ourselves). For that reason they have a place in
our journal – a place that will likely grow in coming
years.
Marilyn Tseng
Editor
References
1 Karnehed N, Tynelius P, Heitmann BL, Rasmussen F. Physical
activity, diet and gene–environment interactions in relation to
body mass index and waist circumference: The Swedish
Young Male Twins Study. Public Health Nutrition 2006; 9(7):
851–858.
2 Salminen M, Lehtima
¨ki T, Fan Y-M, Vahlberg T, Kivela
¨SL.
Apolipoprotein E polymorphism and changes in serum lipids
during a family-based counselling intervention. Public Health
Nutrition 2006; 9(7): 859–865.
M Tseng822
https://doi.org/10.1017/PHN20062001 Published online by Cambridge University Press
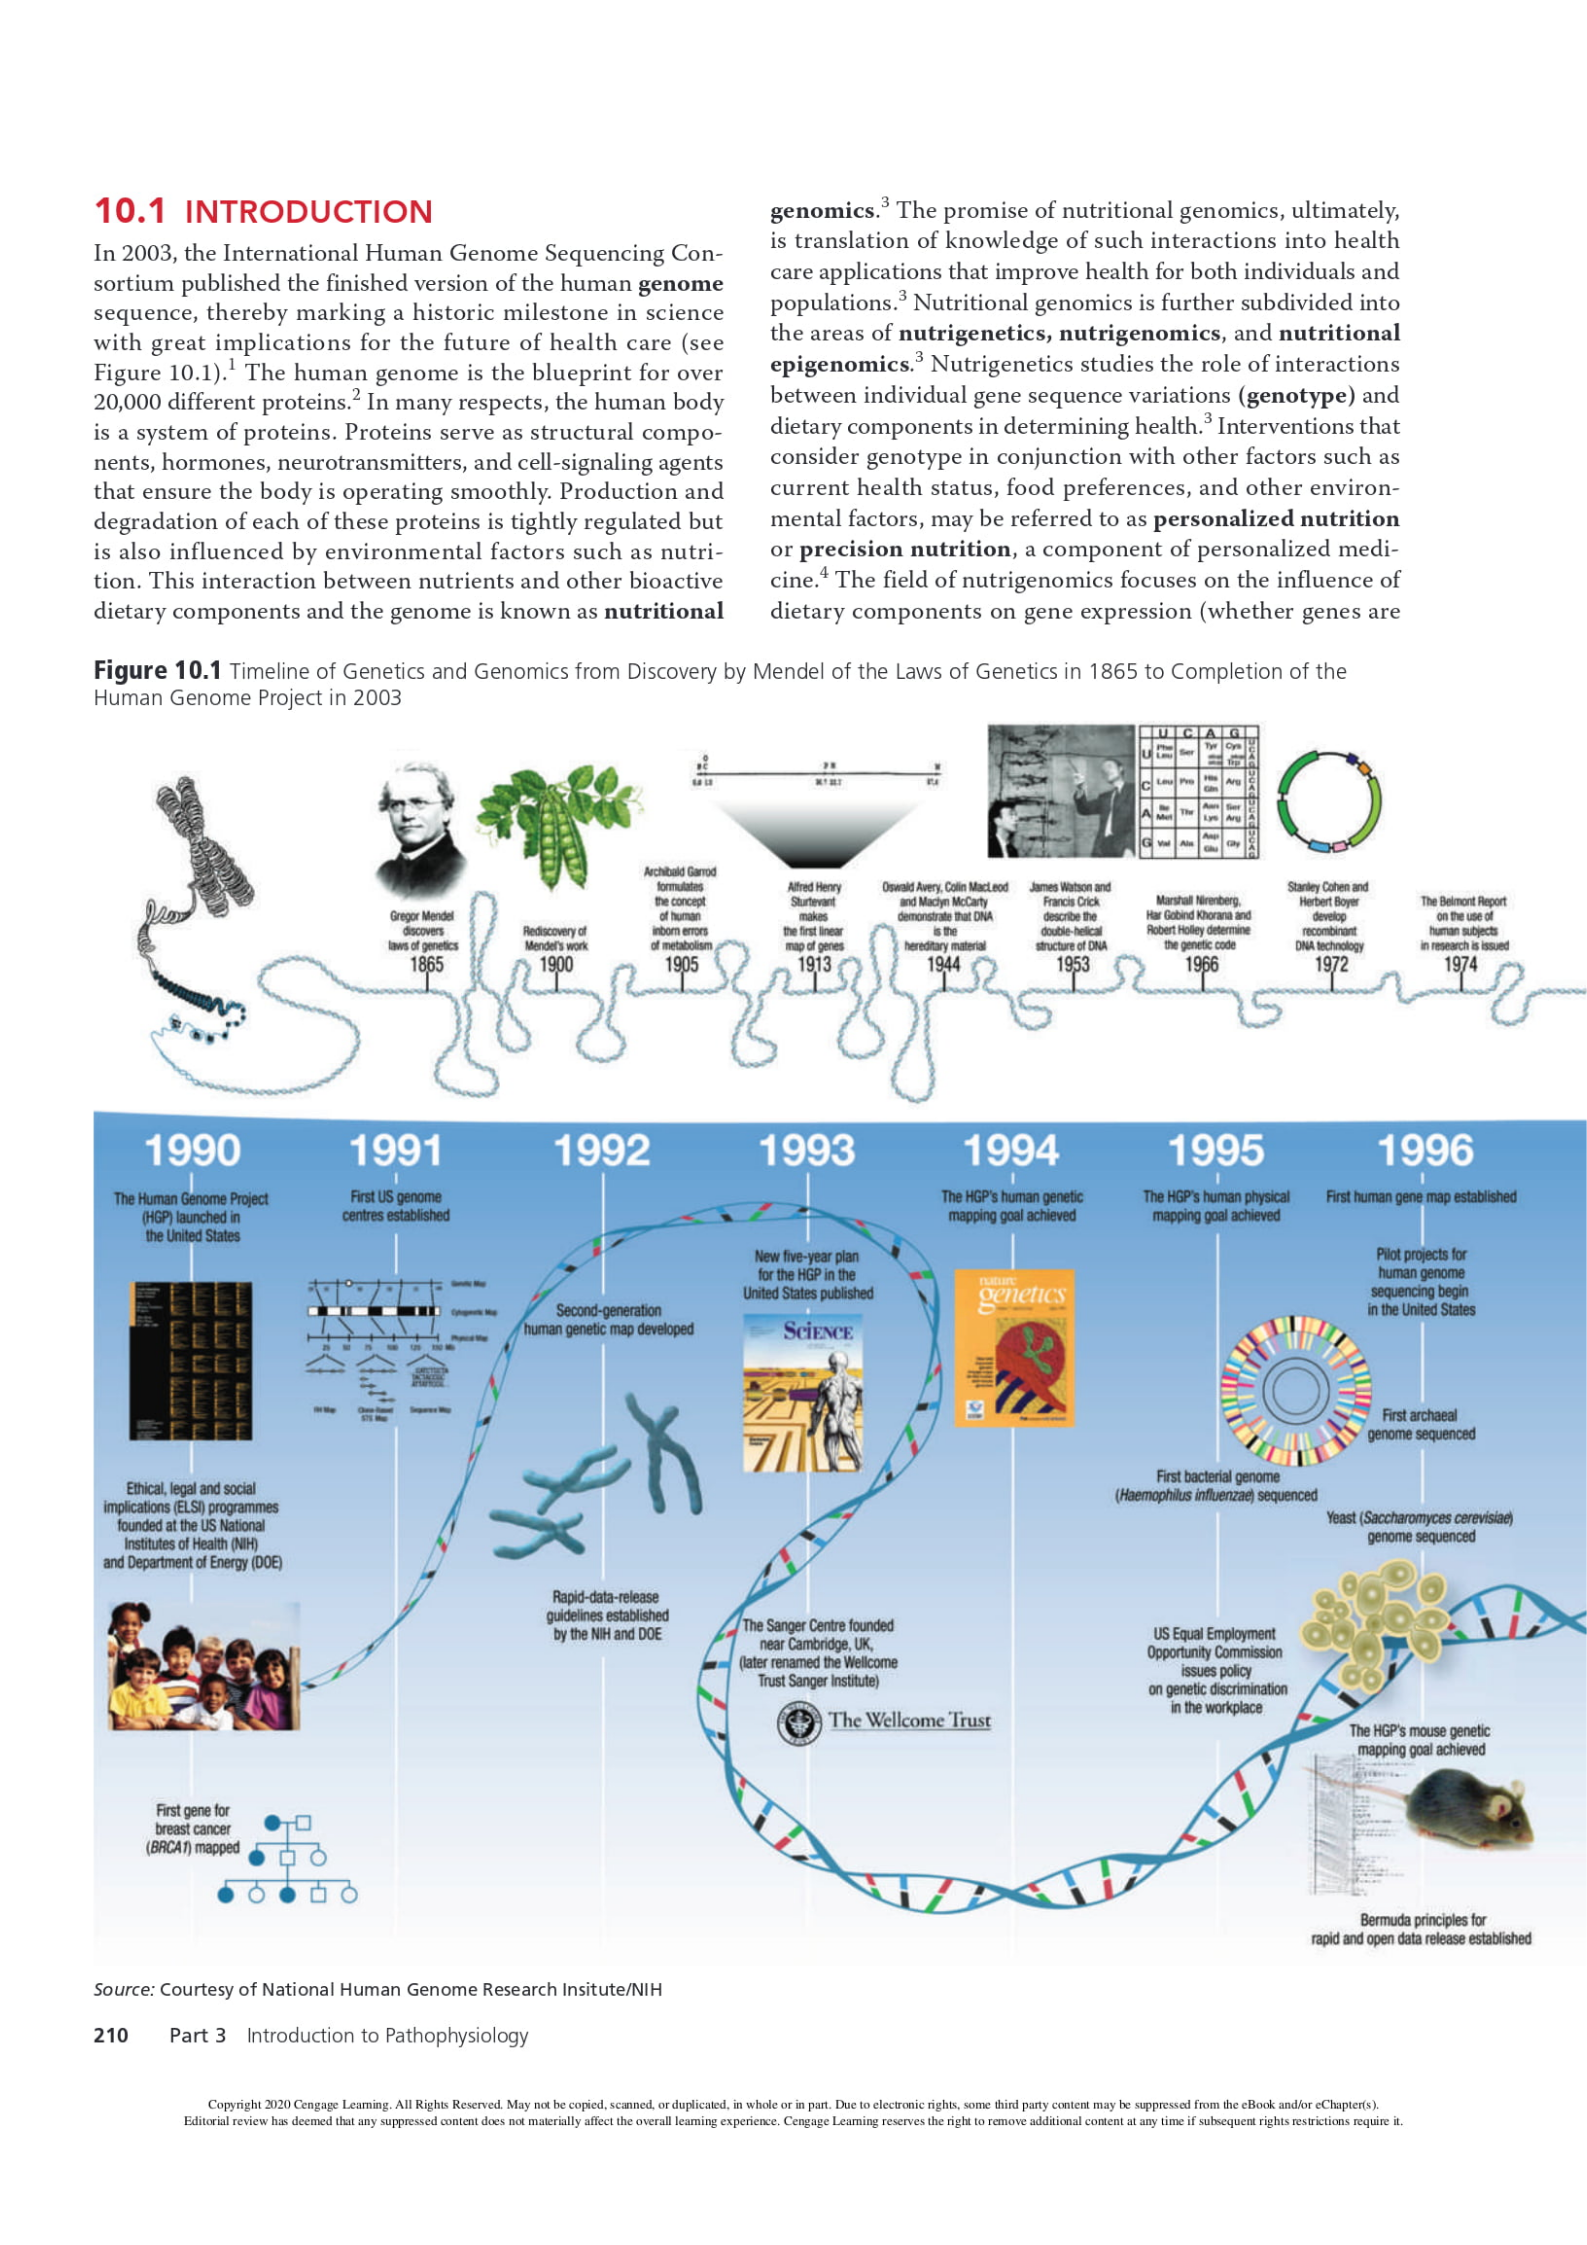
10.1
INTRODUCTION
In
2003,
the
International
Human
Genome
Sequencing
Con-
sortium
published
the
finished
version
of
the
human
genome
sequence,
thereby
marking
a
historic
milestone
in
science
with
great
implications
for
the
future
of
health
care
(see
Figure
10.1).!
The
human
genome
is
the
blueprint
for
over
20,000
different
proteins.”
In
many
respects,
the
human
body
is
a
system
of
proteins.
Proteins serve
as
structural
compo-
nents,
hormones,
neurotransmitters,
and
cell-signaling
agents
that
ensure
the
body
is
operating smoothly.
Production
and
degradation
of
each
of
these
proteins
is
tightly
regulated
but
is
also
influenced
by
environmental
factors
such
as nutri-
tion.
This
interaction
between
nutrients
and
other
bioactive
dietary
components
and
the
genome
is
known
as
nutritional
genomics.’
The
promise
of
nutritional
genomics,
ultimately,
is
translation
of
knowledge
of
such
interactions
into
health
care
applications
that
improve
health
for
both
individuals
and
populations.*
Nutritional
genomics
is
further
subdivided
into
the
areas
of
nutrigenetics,
nutrigenomics,
and
nutritional
epigenomics.’
Nutrigenetics
studies
the
role
of
interactions
between
individual
gene
sequence
variations
(genotype)
and
dietary
components
in
determining
health.’
Interventions
that
consider
genotype
in
conjunction
with
other
factors
such
as
current
health
status,
food
preferences,
and
other
environ-
mental
factors,
may
be
referred
to as
personalized
nutrition
or
precision
nutrition,
a
component
of
personalized
medi-
cine.‘
The
field
of
nutrigenomics
focuses
on
the
influence
of
dietary
components
on
gene
expression
(whether
genes
are
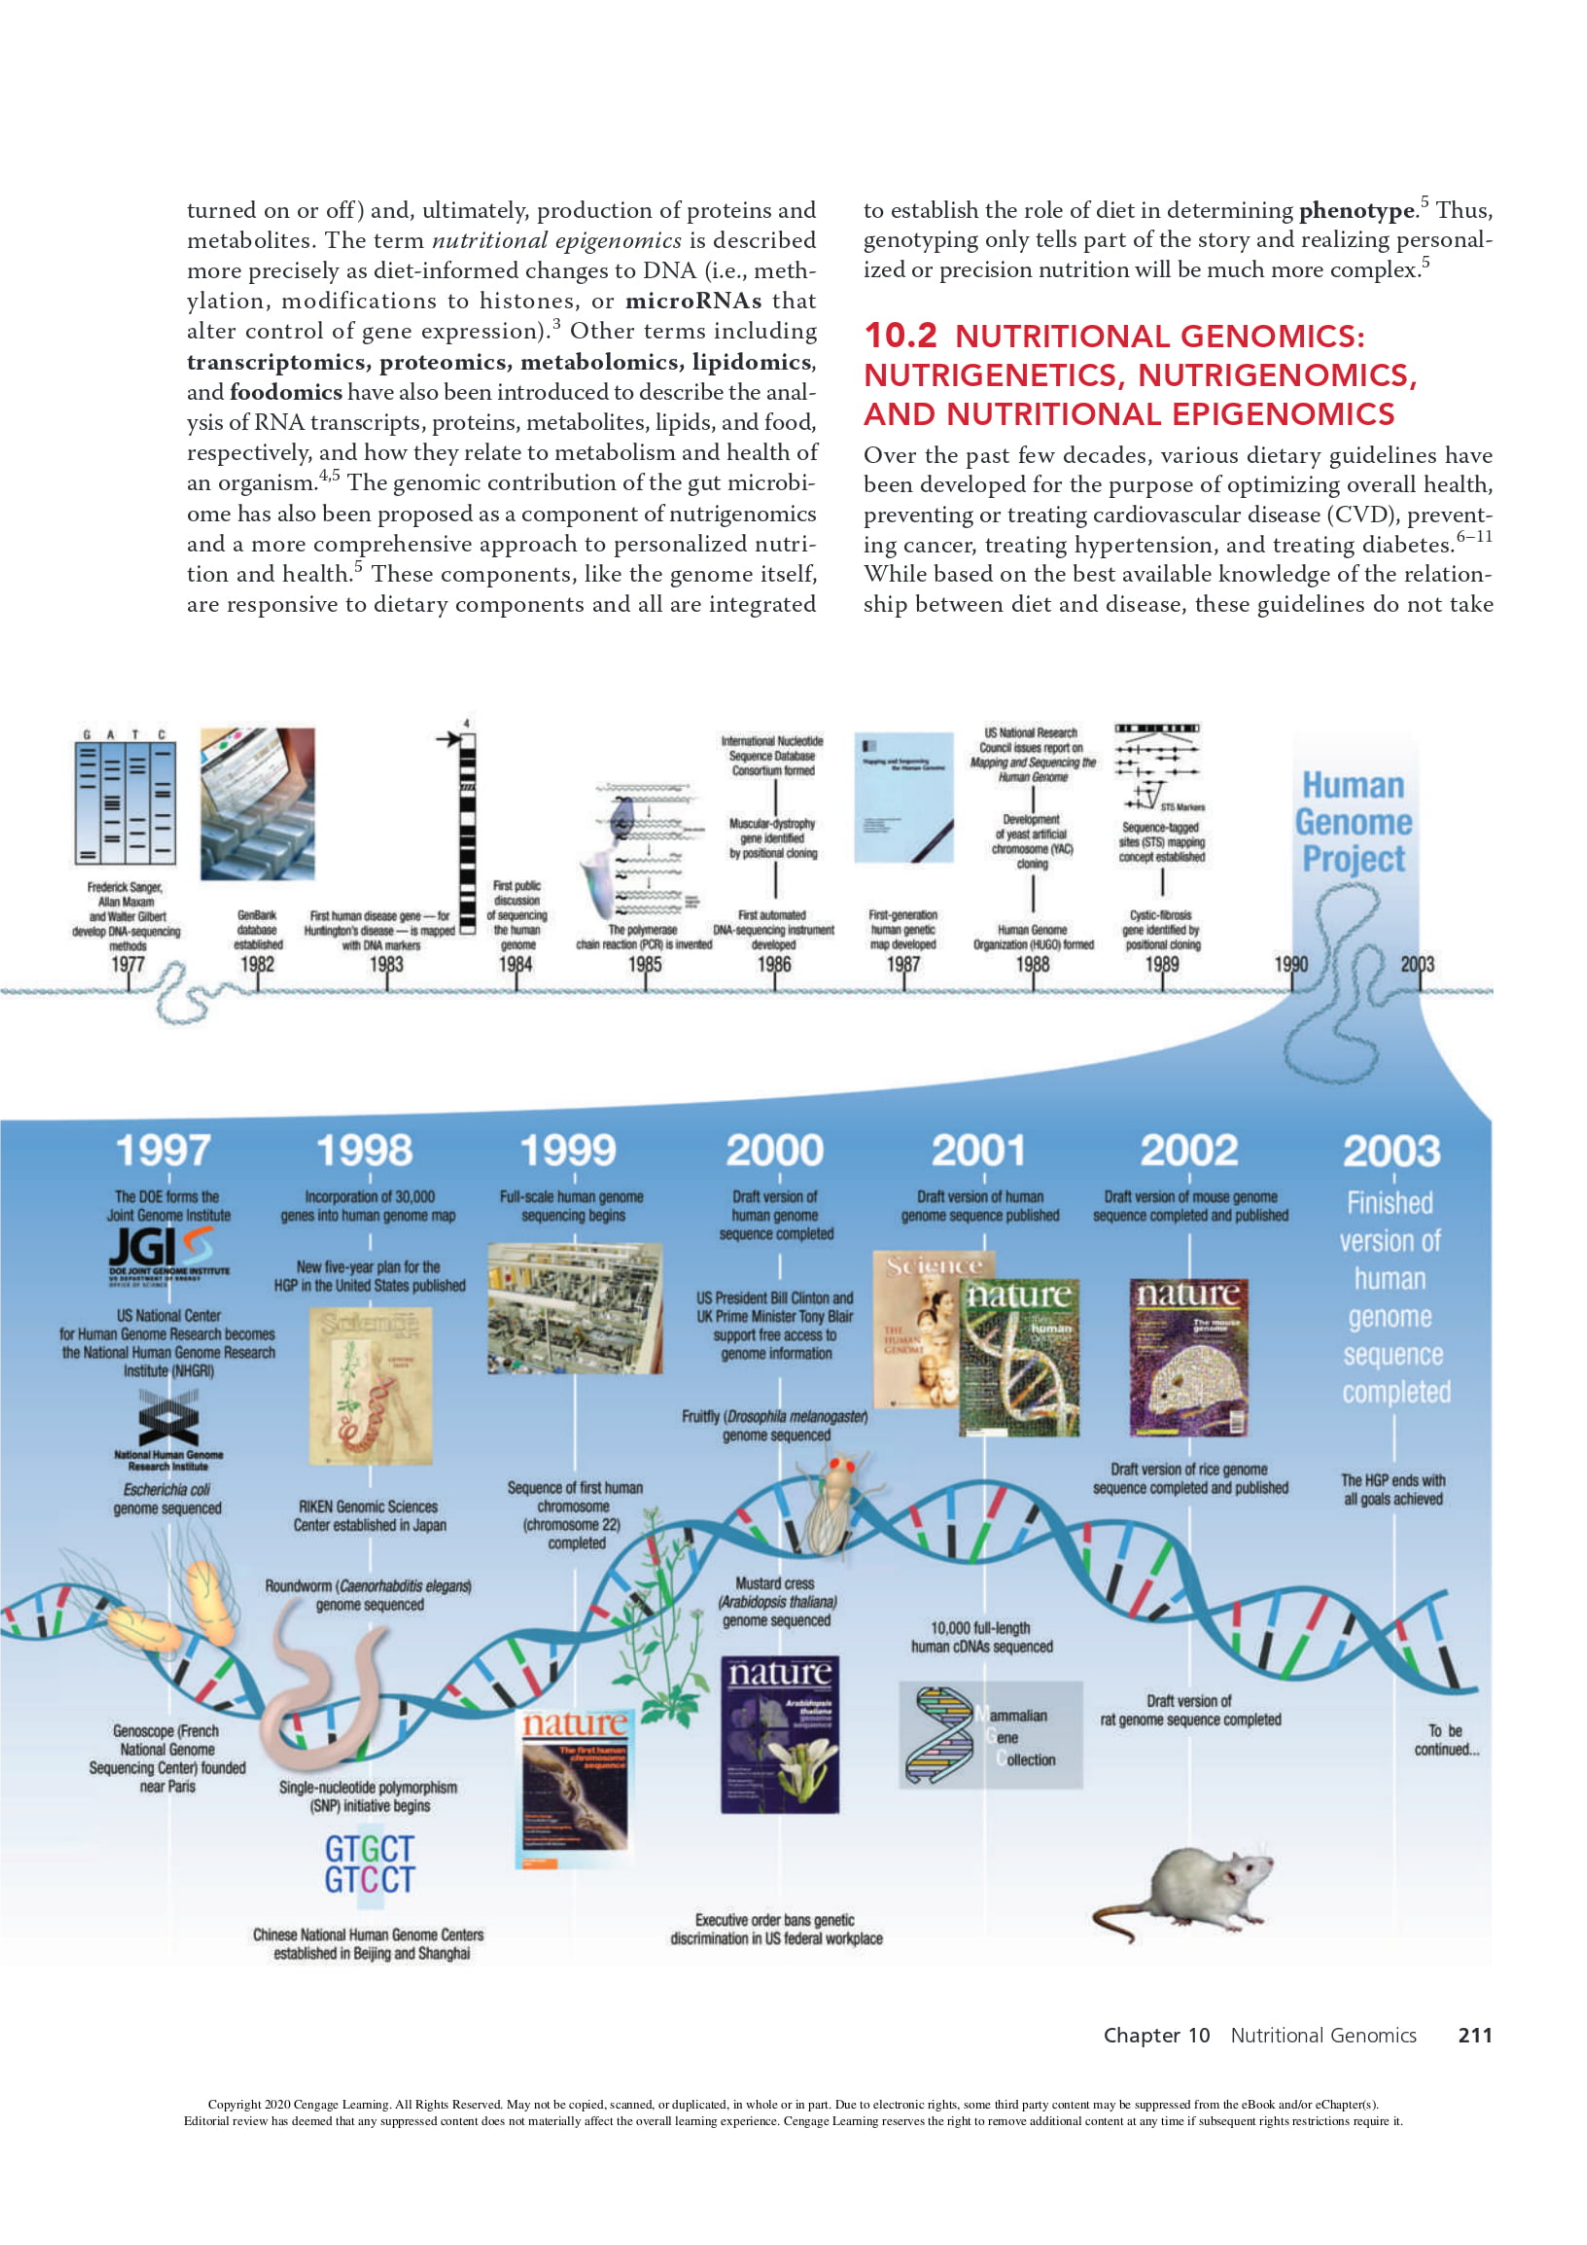
Figure
10.1
Timeline
of
Genetics
and
Genomics
from
Discovery
by Mendel
of
the
Laws
of
Genetics
in
1865
to
Completion
of
the
Human
Genome
Project
in
2003
=
,
‘chibald
Garrod
formusates
‘the
concept
(Gregor
Mende
ot
human
sce
at
‘rbom
errs
(ws
of
genetics
wor,
1992
-
Source:
Courtesy
of
National
Human
Genome
Research
Insitute/NIH
210
Part
3 Introduction to
Pathophysiology
‘Reeanscovery
Mendes
‘of
metabolism
heredtary
material
*
RP
pee
ye
1993
”
a
‘red
Henry
Oswald
Avery,
Colin
Maci.tod
James
Watson
and
‘Sturtevant
‘and
Mactyn
McCarty
Francis
Crick
makes
‘demonstrate
that
OMA
describe
the
‘he
frst
near
ste
‘map
of
genes,
}
Ty
ne)
:
|
prada
t
any
Copyright
2020
Cengage
Leaming.
All
Rights
Reserved.
May
not
be
copied,
scanned,
or
duplicated,
in
whole
or
in
part.
Due
to
electronic
rights,
some
third
party
content
may
be
suppressed
from
the
eBook
and/or
eChapter(s).
Editorial
review
has
deemed
that
any
suppressed
content
does
not
materially
affect
the
overall
learning
experience.
Cengage
Learning
reserves
the
right
toremove
additional
content
at
any
time
if
subsequent
rights
restrictions
requice
it,
Tees
turned
on
or
off)
and,
ultimately,
production
of
proteins
and
metabolites.
The
term
nutritional
epigenomics
is
described
more
precisely
as
diet-informed
changes
to
DNA
(i.e.,
meth-
ylation,
modifications
to
histones,
or
microRNAs
that
alter
control
of
gene
expression).?
Other
terms
including
transcriptomics,
proteomics,
metabolomics,
lipidomics,
and
foodomics
have
also
been
introduced
to
describe
the
anal-
ysis
of
RNA
transcripts,
proteins,
metabolites,
lipids,
and
food,
respectively,
and
how
they
relate
to
metabolism
and
health
of
an
organism.*°
The
genomic
contribution
of
the
gut
microbi-
ome
has
also
been
proposed
as a
component
of
nutrigenomics
and
a
more
comprehensive
approach
to
personalized
nutri-
tion
and
health.®
These
components,
like
the
genome
itself,
are
responsive
to
dietary
components
and
all
are
integrated
to establish
the
role
of
diet
in
determining
phenotype.’
Thus,
genotyping
only
tells
part
of the
story
and
realizing
personal-
ized
or
precision
nutrition
will
be
much
more
complex.
10.2
NUTRITIONAL
GENOMICS:
NUTRIGENETICS,
NUTRIGENOMICS,
AND
NUTRITIONAL
EPIGENOMICS
Over
the
past
few
decades,
various
dietary
guidelines
have
been
developed
for
the
purpose
of
optimizing
overall
health,
preventing
or
treating
cardiovascular
disease
(CVD),
prevent-
ing
cancer,
treating
hypertension,
and
treating
diabetes.°!!
While
based
on
the
best
available
knowledge
of the
relation-
ship
between
diet
and
disease,
these
guidelines
do
not
take
ya
1998 1999
2000
nature
id
4
Executive order
bans
genetic
discrimination
in
US
federal
workplace
P10)
0
21
0)
aI
Suet)
VSO
WE
CT
sequence
Coane)
i
Sc
rere
|
ve
Hature
nature
|
rs
r
a)
Chapter
10
Nutritional
Genomics.
211
Copyright
2020
Cengage
Leaming.
All
Rights
Reserved.
May
not
be
copied,
scanned,
or
duplicated,
in
whole
or
in
part.
Due
to
electronic
rights,
some
third
party
content
may
be
suppressed
from
the
eBook
and/or
eChapter(s).
Editorial
review
has
deemed
that
any
suppressed
content
does
not
materially
affect
the
overall
learning
experience.
Cengage
Learning
reserves
the
right
toremove
additional
content
at
any
time
if
subsequent
rights
restrictions
requice
it,

into
account
the
genetic
and
epigenetic
variation
within
the
population
and
how
that
variation
can
play
a
role
in
individual
response
to
dietary
factors
and,
hence,
health
and
disease.
Such
information
has
heretofore
been
unavailable,
but
completion
of
the
Human
Genome
Project
and
a
heavy
research
emphasis
on.
identifying
the
specific
and
complex
interactions
between
diet
and
the
genome
are
beginning
to
yield
results
while
also
reveal-
ing
the
complexity
of
implementing
precision
nutrition.>
Attention
to
nutritional
genomics
and
pharmacog-
enomics
has
been
escalating,
and
this
trend
is
likely
to
con-
tinue
in
the
coming
years.
For
example,
the
Academy
of
Nutrition
and
Dietetics
(AND)
in
2014
issued
the
first
posi-
tion
paper
on
nutritional
genomics,
and
a
Nutrition
Genom-
ics
Project
is
currently
underway
within
the
AND
Evidence
Analysis
Library.°"?
In the
Academy’s
position,
it
is
stated
that
“...
registered
dietitians
need
basic
competency
in
genetics
as
a
foundation
for
understanding
nutritional
genomics;
profi-
ciency
requires
advanced
knowledge
and
skills.’
It
further
goes
onto
state
that
“the
practical
application
of
nutritional
genomics
for
complex
chronic
disease
is
an
emerging
science
and
the
use
of
nutrigenetic
testing
to
provide
dietary
advice
is
not
ready
for
routine
dietetics
practice.”
In 2017,
a
group
of
leading
researchers
in
nutrigenetics
issued
proposed
guide-
lines
for
evaluation
of
the
scientific
validity
and
current
evi-
dence
for
diet
intervention
based
on
genotype,
noting
the
prevalence
of
unsupported
claims
based
on
genetic
testing
and
the
propensity
of
commercial
purveyors
of
personalized
nutrition
to
oversimplify
information
that
is,
in
reality,
quite
complex.!?
Thus,
while
genomics
holds
great
potential
for
revolutionizing
health
care
and
registered
dietitian
nutrition-
ists
(RDNs) must
be
prepared
with
the
requisite
knowledge
and
skills,
the
solid
evidence
base
that
underlies
other
areas
of
dietetics
practice
must
also
be
established
in
nutritional
genomics.°
Furthermore,
the
advent
of
genomics—including
nutritional
genomics—is
not
without
its
ethical
challenges
(see
Box
10.1).
BOX
10.
RESEARCH
TO
PRACTICE
Ethics
and
the
ELSI
Research
Program
The
National
Human
Genome
Research
Institute
(NHGRI)
estab-
lished
the
Ethical,
Legal
and
Social
Implications
(ELSI)
Research
Program
in
1990
as
a
part
of
the
Human
Genome
Project.'
Its
purpose
is
to
support
research
on
the
ethical,
legal,
and
social
implications
of
genetics
and
genomics
research.
Although
there
is
great
public
interest
in
the
application
of
personal
genetic
knowledge
to
improved
health,
there
is
also
concern
regarding
misuse
of
personal
genetic
information.”
In
May
2008,
the
Genetic
Information
Nondiscrimination
Act
(GINA)
was
signed
into
federal
law
by
President
George
W.
Bush.?
This
legislation
prohibits
insurers
from
requesting
or
requiring
genetic
testing
of
an
individual
or
family,
and
from
using
genetic
information
to
establish
eligibility
or
premiums.
Furthermore,
it
prohibits
employers
from
requesting
or
requiring
genetic
testing
and
from
using
genetic
testing
for
hiring
or
promotional
decisions.?
In
2013,
anew
rule
adopted
by
the
U.S.
Department
of
Health
and
Human
Services
filled
some
of
the
gaps by
extending
pro-
tections
to
Medicare,
Medicaid,
the
Indian
Health
Service,
and
other
programs.*
While
the
passage
of
GINA
is
a
step
in
the
right
direction,
it
does
not
cover
life,
long-term
nursing
home
care,
or
disability
insurance
and
the
application
of
genomics
itself
can
still
be an
ethical
minefield.
For
example,
examining
the
complex
relation-
ship
of
genomics
with
race,
ethnicity,
and
behavioral
character-
istics
goes
beyond
studying
the
relationship
of
the
genome
to
disease
propensity.
Linking
specific
genotypes
to
intelligence
or
sexual
orientation,
for
example,
has
the
potential
to
overstate
the
role
of
genetics
and
confer
stigmatization
by
suggesting
alleles
associated
with
perceived
negative
traits
are
more
com-
mon
in
some
populations
than
in
others.
Thus,
the
implications
for
individuals
and
society
in
uncovering
the
genomic
contri-
bution to
specific
behaviors
or
traits
are
immense.
These
impli-
cations
must be
considered,
along
with
input
from
a
diverse
group
of
individuals
and
organizations,
before
such
research
is
undertaken.”
In
2011,
the
NHGRI
published
their
most
recent
strategic
plan,
which
includes
a
section
on
“Genomics
and
Society,”
delineating
a
number
of
psychosocial,
ethical,
legal
and
public
policy,
and
broad
societal
issues
related
to
genomics.'?
In
2018,
they
announced
the
launch
of
the
latest
strategic
planning
process
with
expected
issue
of
the
new
stra-
tegic
plan
in
October
of
2020.
As
part
of
this
new
plan,
NHGRI
expects
ongoing
emphasis
in
several
areas,
including
ethical,
legal,
and
social
implications
of
genomics.°
The
ELS!
Research
Program
funds
and
manages
research
and
also
supports
work-
shops,
research
consortia,
and
policy
conferences
related
to
these
NHGRI
priority
areas:
Genetic
and
genomic
research.
This
area
includes
issues
related
to protection of
human
research
participants
(i.e.,
privacy
and
identifiability
of
genetic
information),
recruit-
ment
of
diverse
participants
in
genomics
research,
commu-
nity
engagement,
and
other
related
areas.
¢
Genetic
and
genomic
health
care.
This
area
includes
util-
ity
of
genomic
health
information
at
personal
and
clinical
levels,
fair
access,
economic
considerations
such
as
cost
effectiveness
and
reimbursement,
public health
applica-
tions, rights
of
patients
and
their
families,
laboratories,
and
health
care
providers,
various
ethical
issues
including
impact
of
results
and
patient
health
behaviors
and
outcomes,
and
attending
to
issues
associated
with
genetic
diagnoses
pre-implantation,
prenatally,
and
postnatally,
and
other
related
areas.
¢
Broader
legal,
policy,
and
societal
implications.
This
area
includes
a
number
of
issues
related
to
the
role
of
the
Citizen
Science
movement
including
patient-driven
medicine,
regulation
of
emerging
genomic
technologies,
potential
harmful
effects
of
genetic
determinism
on
pub-
lic
attitudes
and
policies,
and
how
increasing
genomic
knowledge
will
change
understanding
of
race,
ethnicity,
and
identity
and
relationships
both
within
and
among
human
populations,
human
relationships
with
nonhumans,
and
human
origins.
It
further
addresses
nonmedical
uses
of
genomic
information
including
areas
such
as
ancestry
testing,
insurance
eiigibility,
and
criminal
responsibility.
212
Part
3 Introduction to
Pathophysiology
Copyright
2020
Cengage
Leaming.
All
Rights
Reserved.
May
not
be
copied,
scanned,
or
duplicated,
in
whole
or
in
part.
Due
to
electronic
rights,
some
third
party
content
may
be
suppressed
from
the
eBook
and/or
eChapter(s).
Editorial
review
has
deemed
that
any
suppressed
content
does
not
materially
affect
the
overall
leaming
experience.
Cengage
Learning
reserves
the
right
to
remove
additional
content
at
any
time
if
subsequent
rights
restrictions
requive
it.

One
of
the
hottest
areas
of
debate
regarding
the
interplay
between
ethics
and
genetics
has
to
do
with
direct-to-consumer
(DTC)
marketing
of
genetic
tests.®
After
completion
of
the
Human
Genome
Project,
direct
marketing
companies
began
offering
genetic
testing
directly
to
consumers
over
the
Internet,
thereby
bypassing
health
care
providers.
Health
care
practice,
particularly
in
clinical
genetics,
is
very
focused
on
informed
con-
sent,
confidentiality,
and
appropriate
counseling
and
guidance
regarding
test
results.’
These
elements
are
often
missing
in
the
DTC
environment,
potentially
misleading
consumers
and
result-
ing
in
inappropriate
health care
choices.
Consumers
may
also
be
subject
to
dubious
interpretation
of
scant
research
regard-
ing
the
strength
of
relationships
between
specific
genes
and
disease.
Twenty companies
were
offering
DTC
genetic
testing
in
2011,
with
an
additional
seven
offering
DTC
genetic
testing
through
a
physician.
However,
in
the
intervening
years,
the
DTC
genetic
testing
landscape
has
experienced
an
upheaval.
In
late
November
of
2013,
the
FDA
issued
a
letter
requiring
high
profile
DTC
company
23andMe
to
discontinue
marketing
of
their
Personal
Genome
Service,
calling
it
a
violation
of
the
Federal
Food,
Drug,
and Cosmetic
Act
due
to
its
being
mar-
keted
as
a
medical
device.
The
company
was
forced
to
take
all
health-related
testing
off
the
market
for
a
time,
but
has
since
gone
through
FDA
approval
and
began
offering
limited
genetic
health
risk
testing
in
the
DTC
market
in
2017.°
The
10
diseases
and
conditions
addressed
through
these
tests
include
Parkinson's
Disease,
late-onset
Alzheimer’s
Disease,
celiac
disease,
and
a
few
blood
conditions
among
others.
In
2018
23andMe
gained
approval to
add
a
health
risk
test
for
3
variants
of
BRCA1/BRCA2,
genes
linked
to
breast
cancer
risk.'°
A
key
distinction
is
that
the
testing
offered
can
be
used
to
predict
risk,
but
cannot be
used
for
diagnostic
purposes.?
Despite
DTC
changes,
myriad
concerns remain
regarding
the
need
for
regulation
of
privacy
in
use
of
genetic
information.
'!
For
example,
it
is
possible
for
someone
other
than
the
sample
source
to
submit
a
genetic
sample
without
consent
first
being
obtained.
For
further
exploration
of
ethics
specifically
relating
10.3
AN
OVERVIEW
OF
THE
STRUCTURE
AND
FUNCTION
OF
GENETIC
MATERIAL
Deoxyribonucleic
Acid
and
Genome
Structure
While
Mendel,
the
father
of
modern-day
genetics,
discovered
the
laws
of genetics
in
1865,
deoxyribonucleic
acid
(DNA)
was
not
itself
identified as
the
blueprint
of
life
until
1944,
and
its
double-helical
structure
was
not
discovered
until
1953.!*
DNA
makes
up
the
genome,
which
does
not
itself
build
an
organism,
but
provides
the
instructions
that
tell
how
to
build
an
organism.
From
a
human
perspective,
the
genes
contained
in
each
person’s
DNA
encode
essentially
the
same
proteins,
but
this
code
varies
from
person
to
person,
thus
yielding
inherited
differences
in
physical
characteristics,
intellect,
and
behavioral
characteristics
as
well
as
the
propensity
for
devel-
oping
disease.!*
Ethics
and
the
ELSI
Research
Program
(continued)
to
nutritional
genomics,
see
the
section
“Nutritional
Genomics
and
the
Practice
of
Dietetics”
near
the
end
of
this
chapter.
References
1.
National
Human
Genome
Research
Institute
(NHGRI),
ELSI
Research
Program.
The
Ethical,
Legal
and
Social Implications
(ELSI)
Research
Program.
Bethesda,
MD:
NHGRI;
2018.
https://(www.genome
-gov/10001618/the-elsi-research-program/.
2.
Green
ED,
Guyer
MS,
National
Human
Genome
Research
Institute.
Charting
a
course
for
genomic
medicine
from
base
pairs
to
bedside.
Nature.
2011;
470:204-13.
3.
National
Human
Genome
Research
Institute
(NHGRI).
Genetic
Discrimination.
Bethesda,
MD:
NHGRI;
2017.
https:/Avww.genome
-gov/10002077/genetic-discrimination/.
4.
Department
of Health
and
Human
Services.
Modifications
to
the
HIPAA
Privacy,
Security,
Enforcement,
and
Breach
Notification
Rules
Under
the
Health
Information
Technology
for
Economic
and
Clinical
Health
Act
and
the
Genetic
Information
Nondiscrimina-
tion
Act;
Other
Modifications
to
the
HIPAA
Rules.
Fed.
Reg.
Jan.
25,
2013;
78:5565-702.
http:/Awww.gpo.gov/fdsys/pkg/FR-2013-
01-25/pdf/2013-01073.pdf.
5.
National
Human
Genome
Research
Institute
(NHGRI).
Strategic
Plan-
ning:
Overview.
Bethesda,
MD:
NHGRI;
2018.
https://www.genome
.gov/27570607/strategic-planning-overview/.
6.
Hogarth
S,
Javitt
G,
Melzer
D.
The
current
landscape
for
direct-to-
consumer
genetic
testing:
Legal,
ethical,
and
policy
issues.
Ann
Rev
Genomics
Hum
Genet.
2008;
9:16
1-82.
7.
ACMG
Board
of
Directors.
Direct-to-consumer
genetic
testing:
a
revised
position
statement
of
the
American
College
of
Medical
Genetics
and
Genomics.
Genet
Med.
2016;
18(2):207-8.
8.
U.S.
Food
and Drug
Administration.
Inspections,
Compliance,
Enforcement,
and
Criminal
Investigations.
23andMe,
Inc.
11/22/13.
Silver
Spring,
MD:
U.S.
Food and Drug
Administration;
2013.
http://
www.
fda.goviC
EC
/EnforcementActions/WarningLetters/2013/
ucm376296.htm.
9.
U.S.
Food and Drug
Administration.
FDA
Allows
Marketing
of
First
Direct-to-Consumer
Tests
that
Provide
Genetic
Risk
Information
for
Certain
Conditions.
4/6/2017.
Silver
Spring,
MD:
U.S.
Food and
Drug
Administration;
2018.
https://www.fda.gov/NewsEvents/
Newsroom/PressAnnouncements/ucm551185.htm.
10.
U.S.
Food and Drug
Administration.
FDA
Authorizes,
with
Special
Controls,
Direct-To-Consumer
Test
that
Reports
Three
Mutations
in
the
BRCA
Breast
Cancer
Genes.
3/6/2018.
Silver
Spring,
MD:
U.S.
Food and Drug
Administration;
2018.
https://www.fda.gow/NewsEv-
ents/Newsroom/PressAnnouncements/ucm599560.htm.
11.
May
T.
Sociogenetic
risks—ancestry
DNA
testing,
third-party
iden-
tity,
and
protection
of
privacy.
N
Eng!
J
Med.
2018.
doi:
10.1056/
NEJMp1805870.
The
genetic
material
or
genome
lies
within
each
nucleus
of
each
cell
in
the
body
(except
mature
red
blood
cells,
which
do
not
contain
nuclei).!*
In
humans,
the
genome
comprises
23
pairs
of
chromosomes.
During
mitosis
(cell
division)
within
an
individual,
all
23
pairs
of
chromosomes
are
copied
during
the
creation
of
a
new
daughter
cell.
During
meiosis
(reproduction),
only
one
member
of
each
pair
of
chromo-
somes
is
passed
on
to
each
ovum
or
sperm
cell;
the
result
is
offspring
that
contain
chromosomal
pairs
created
by
the
donation
of
one
copy
of
each
chromosome
from
each
parent.
Of
the
23
pairs,
22
are
autosomes
and
one
pair
comprises
of
the
sex
chromosomes.
Males
have
one
X
and one
Y
chromo-
some,
while
females
have
two
X
chromosomes,
so the
gender
of
offspring
is
determined
by
the
sex
chromosome
passed
on
by
the
male
parent.
Each
chromosome
consists
of
DNA
con-
taining
a
linear
sequence
of genes,
each
encoding
a
specific
Chapter
10
Nutritional
Genomics.
213
Copyright
2020
Cengage
Leaming.
All
Rights
Reserved.
May
not
be
copied,
scanned,
or
duplicated,
in
whole
or
in
part.
Due
to
electronic
rights,
some
third
party
content
may
be
suppressed
from
the
eBook
and/or
eChapter(s).
Editorial
review
has
deemed
that
any
suppressed
content
does
not
materially
affect
the
overall
leaming
experience.
Cengage
Learning
reserves
the
right
to
remove
additional
content
at
any
time
if
subsequent
rights
restrictions
require
it.

protein.
The
copy
of
each
gene
inherited
from
the
father
is
the
paternal
allele,
and
the
one
inherited
from
the
mother
is
the
maternal
allele.
Each
gene
inhabits
a
particular
location
ona
particular
chromosome
called
its
“locus.”
For
example,
Figure
10.2
shows
a
map
of
chromosome
10
that
identifies
the
location
of
defects
on
this
chromosome
associated
with
spe-
cific
disease
states.
Each
gene
is
itself
a
linear
sequence
of
nucleotides
that
are
actually
responsible
for
encoding
proteins
(see
Figure
10.2
Chromosome
10
Figure
10.3).
Nucleotides
have
three
primary
components:
a
purine
or
pyrimidine
nitrogenous
base,
a
ribose
(a
pen-
tose
sugar),
and
a
phosphate
group.
The
backbone
of
the
chain
is
an
alternating
strand
of
the
ribose
and
phosphate
residues.
The
nitrogenous
bases
project
from
this
backbone
and
include
adenine
(A)
and
guanine
(G)
(both
purines)
as
well
as
thymine
(T)
and
cytosine
(C),
which
are
both
pyrim-
idines.
As DNA,
this
chain
is
paired
with
a
complementary
strand
in
which
As
always
pair
with
Ts
and
Gs
always
pair
Sequencing
and
analysis
of
human
chromosomes
have
enabled
researchers
to
characterize
in
detail
a
number
of
genes
associated
with
diseases.
Identifying
the
genes
on
all
human
chromosomes
offers
scientists
worldwide
an
invaluable
resource
for
improving
human
health
and
combating
disease.
Knowledge
about
genes
will
increase
understanding
of
how
genetics
influences
the
development
of
disease,
help
researchers
find
genes
associated
with
particular
diseases,
and
aid
in
the
identification
of
appropriate
dietary
interventions
and
development
of
new
pharmaceuticals.
Chromosome
10
(pictured
here)
includes
700-800
genes
and
has
been
linked
to
various
disease
states
with
nutritional
implications
including
several
cancers,
type
1
diabetes,
and
Crohn's
disease.
disease,
adult
renal
dysplasia
facial
syndrome
Leukemia
rombocytopenia
thyroid
oncogene
Ewing
Sarcoma
Obesity,
susceptibility
to
Multiple
endocrine
neoplasia
Medullary
thyroid
carcinoma
Hirschsprung
disease
Thyroid
papillary
carcinoma
Deafness,
autosomal
recessive
Serotonin
receptor
Moebius
syndrome
Hemolytic
anemia
Hyperphenylalaninemia
Metachromatic
leukodystrophy
Gaucher
disease,
variant
form
SEMD,
Pakistani
type
Hermansky-Pudlak
syndrome
Breast
cancer
Multiple
advanced
cancers
Cowden
disease
Lhermitte-Duclos
syndrome
Bannayan-Zonana
syndrome
Endometrial
carcinoma
Polyposis,
juvenile
intestinal
Prostate
cancer
Progressive
external
ophthalmoplegia
Corneal
dystrophy,
Thiel-Behnke
type
Leukemia,
T-cell
acute
lymphocytic
Spinocerebellar
ataxia,
infantile-onset
Split
hand/foot
malformation,
type 3
Polycystic
kidney
disease
Meningioma-expressed
antigen
Adrenal
hyperplasia,
congenital
Diabetes
mellitus,
insulin-dependent
Anterior
segment
mesenchymal
dysgenesis
Cataract,
congenital
Malignant
brain
tumors
Glioblastoma
multiforme
Medulloblastoma
Crouzon
syndrome
Jackson-Weiss
syndrome
Beare-Stevenson
cutis
gyrata
syndrome
214
Part
3 Introduction to
Pathophysiology
135
million
base
pairs
Suppression
of
tumorigenicity,
prostate
Prostate
adenocarcinoma
Interleukin
receptor,
alpha
chain,
deficiency
of
Arrhythmogenic
right
ventricular
dysplasia
Myasthenic
antigen
B
Lambert-Eaton
syndrome
Megaloblastic
anemia
Diabetes
mellitus,
insulin-dependent
Severe
combined
immunodeficiency
disease,
Athabascan
Cockayne
syndrome,
type
B
Cerebrooculofacioskeletal
syndrome
Opsonic
defect
Chronic
infections
Retinal
nonattachment,
nonsyndromic
congenital
Cardiomyopathy,
dilated,
autosomal
dominant
Neuropathy,
congenital
hypomyelinating
Graves
disease
autoantigen
Hypermethioninemia,
persistent,
autosomal
dominant
Hemophagocytic
lymphohistiocytosis,
familial
Retinitis
pigmentosa,
autosomal
recessive
and
dominant
Urofacial
syndrome
(Ochoa
syndrome)
Hypoglobulinemia
and
absent
B
cells
Hyperinsulinism-hyperammonemia
syndrome
Spastic
paraplegia
Dubin-Johnson
syndrome
Warfarin
sensitivity
Wolman
disease
Cholesteryl
ester
storage
disease
Tumor
necrosis
factor
receptor
superfamily,
member
6
Autoimmune
lymphoproliferative
syndrome
Epidermolysis
bullosa,
generalized
atrophic
benign
Optic
nerve
coloboma
with
renal
disease
Prostate
cancer
Neurofibrosarcoma
Porphyria,
congenital
erythropoietic
Endometrial
carcinoma
Gyrate
atrophy
of
choroid
and
retina
Pancreatic
lipase
deficiency
Glaucoma
Pfeiffer
syndrome
Apert
syndrome
Saethre-Chotzen
syndrome
Schizencephaly
Polykaryocytosis
inducer
(promoter)
Usher
syndrome,
autosomal
recessive,
severe
Copyright
2020
Cengage
Leaming.
All
Rights
Reserved. May
not
be
copied,
scanned,
or
duplicated,
in
whole
or
in
part.
Due
to
electronic
rights,
some
third
party
content
may
be
suppressed
from
the
eBook
and/or
eChapter(s).
Editorial
review
has
deemed
that
any
suppressed
content
does
not
materially
affect
the
overall
leaming
experience.
Cengage
Learning
reserves
the
right
to
remove
additional
content
at
any
time
if
subsequent
rights
restrictions
requice
it.

Figure
10.3
Nucleotides
within
the
DNA
Molecule
The
four
nitrogenous
bases
of
DNA
are
arranged
along
the
sugar-phosphate
backbone
in
a
particular
order,
encoding
all
genetic
instructions
for
an
organism.
Adenine
(A)
pairs
with
thymine
(T),
while
cytosine
(C)
pairs
with
guanine
(G).
The
two
DNA
strands
are
held
together
codon,
encodes
a
specific
amino
acid.
Thus,
a
specific
sequence
of
nucleotides
(the
genetic
code)
translates
into
a
specific
chain
by
weak
bonds
between
the
bases.
Deoxyribonucleic
Acid
(DNA)
|
Base
Pairs
|
Hydrogen
bonds
Cytosine
Guanine
Be
s'
j—H—-—----
0.
Phosphate
H
°
7
a
He
O=P-O—CHy
4
GC
Weecceue
°
H-N
H
Thymine
CHs
f
Gare
#
Oo
CH
oO
!
Hydroxyl
with
Cs
to
form
a
double-stranded
molecule.
The
DNA
is
tightly
twisted
into
a
double-helical
form,
which
makes
each
chromosome
extremely
compact.!>
Translating
the
Message
from
DNA
to
Protein
The
Genetic
Code
The
code
responsible
for
translation
of
DNA
into
proteins
was
identified
as
a
triplet
code
in
1961.
In
other
words,
a series
of
three
nucleotide
bases,
called
a
of
amino
acids.
This
specific
chain
of
amino
acids
is
a
protein.
Proteins
have
various
functions,
including
serving
as
hormones,
enzymes,
receptors,
transporters,
cell-signaling
agents
(transcrip-
tion
factors,
etc.),
and
antibod-
ies.
Table
10.1
shows
how
each
of
the
64
codons
translates
into
its
respective
amino
acid.
Note
that
in
place
of
the
“T”
base
there
is
a
“U”
for
uracil,
which
takes
the
place
of
thymine
in
RNA
during
the
process
of
creating
a
protein!
DNA
also
contains
noncod-
ing
regulatory
sequences
called
promoter
regions
to
which
mol-
ecules
can
bind
in
order
to
signal
unwinding
of
a
specific
region
of
DNA
for
creation
of
a
needed
protein.
Furthermore,
over
95%
of
DNA
in
humans
is
made
up
of
noncoding
DNA,
which
lies
within
or
in
between
expressed
3
genes.
Due
to
the
apparent
lack
of
purpose,
noncoding
DNA
was
initially
classified
as
“junk
DNA?’!*15
This
view
has
been
challenged
in
recent
years
as
researchers
continue
to
identify
1
functions
of
these
noncoding
regions.
For
example,
numerous
sections
of
noncoding
DNA
have
been
found
to
be
transcribed
into
RNA,
but
this
does
not
result
in
production
of
proteins.
These
noncoding
RNA
sequences
or
microRNAs
(miRNAs)
bind
to
mRNA
to
block
translation
of
the
mRNA
into
protein,
thus
con-
=
trolling cellular
processes
such
1
as
the
cell
cycle,
cell
death,
and
9
tumor
development.'¢
In
short,
t
noncoding
DNA
appears
to
play
fhioaptale
a
largely
regulatory
role.
A
2017
review
identifies
that
60%
of
protein-coding
genes
are
regulated
by
miRNAs
and
nearly
2000
miRNAs
are
encoded
by
the
human
genome.”
Expres-
sion
of
these
miRNAs
may
be
affected
by
diet,
and,
addition-
ally,
both
endogenous
and
diet-derived
microRNAs
may
have
biological
effects,”
Research
suggests
miRNAs
play
a
role in
the
metabolic
response
to
chronic
inflammatory
conditions.!”
So
rather
than
much
of
the
genome
being
classified
as
“junk
DNA,’
the
Encyclopedia
of
DNA
Elements
(ENCODE)
Proj-
ect
found
that
most
of
the
human
genome
(80.4%)—much
Chapter
10
Nutritional
Genomics.
215
Copyright
2020
Cengage
Leaming.
All
Rights
Reserved.
May
not
be
copied,
scanned,
or
duplicated,
in
whole
or
in
part.
Due
to
electronic
rights,
some
third
party
content
may
be
suppressed
from
the
eBook
and/or
eChapter(s).
Editorial
review
has
deemed
that
any
suppressed
content
does
not
materially
affect
the
overall
leaming
experience.
Cengage
Learning
reserves
the
right
to
remove
additional
content
at
any
time
if
subsequent
rights
restrictions
requive
it.
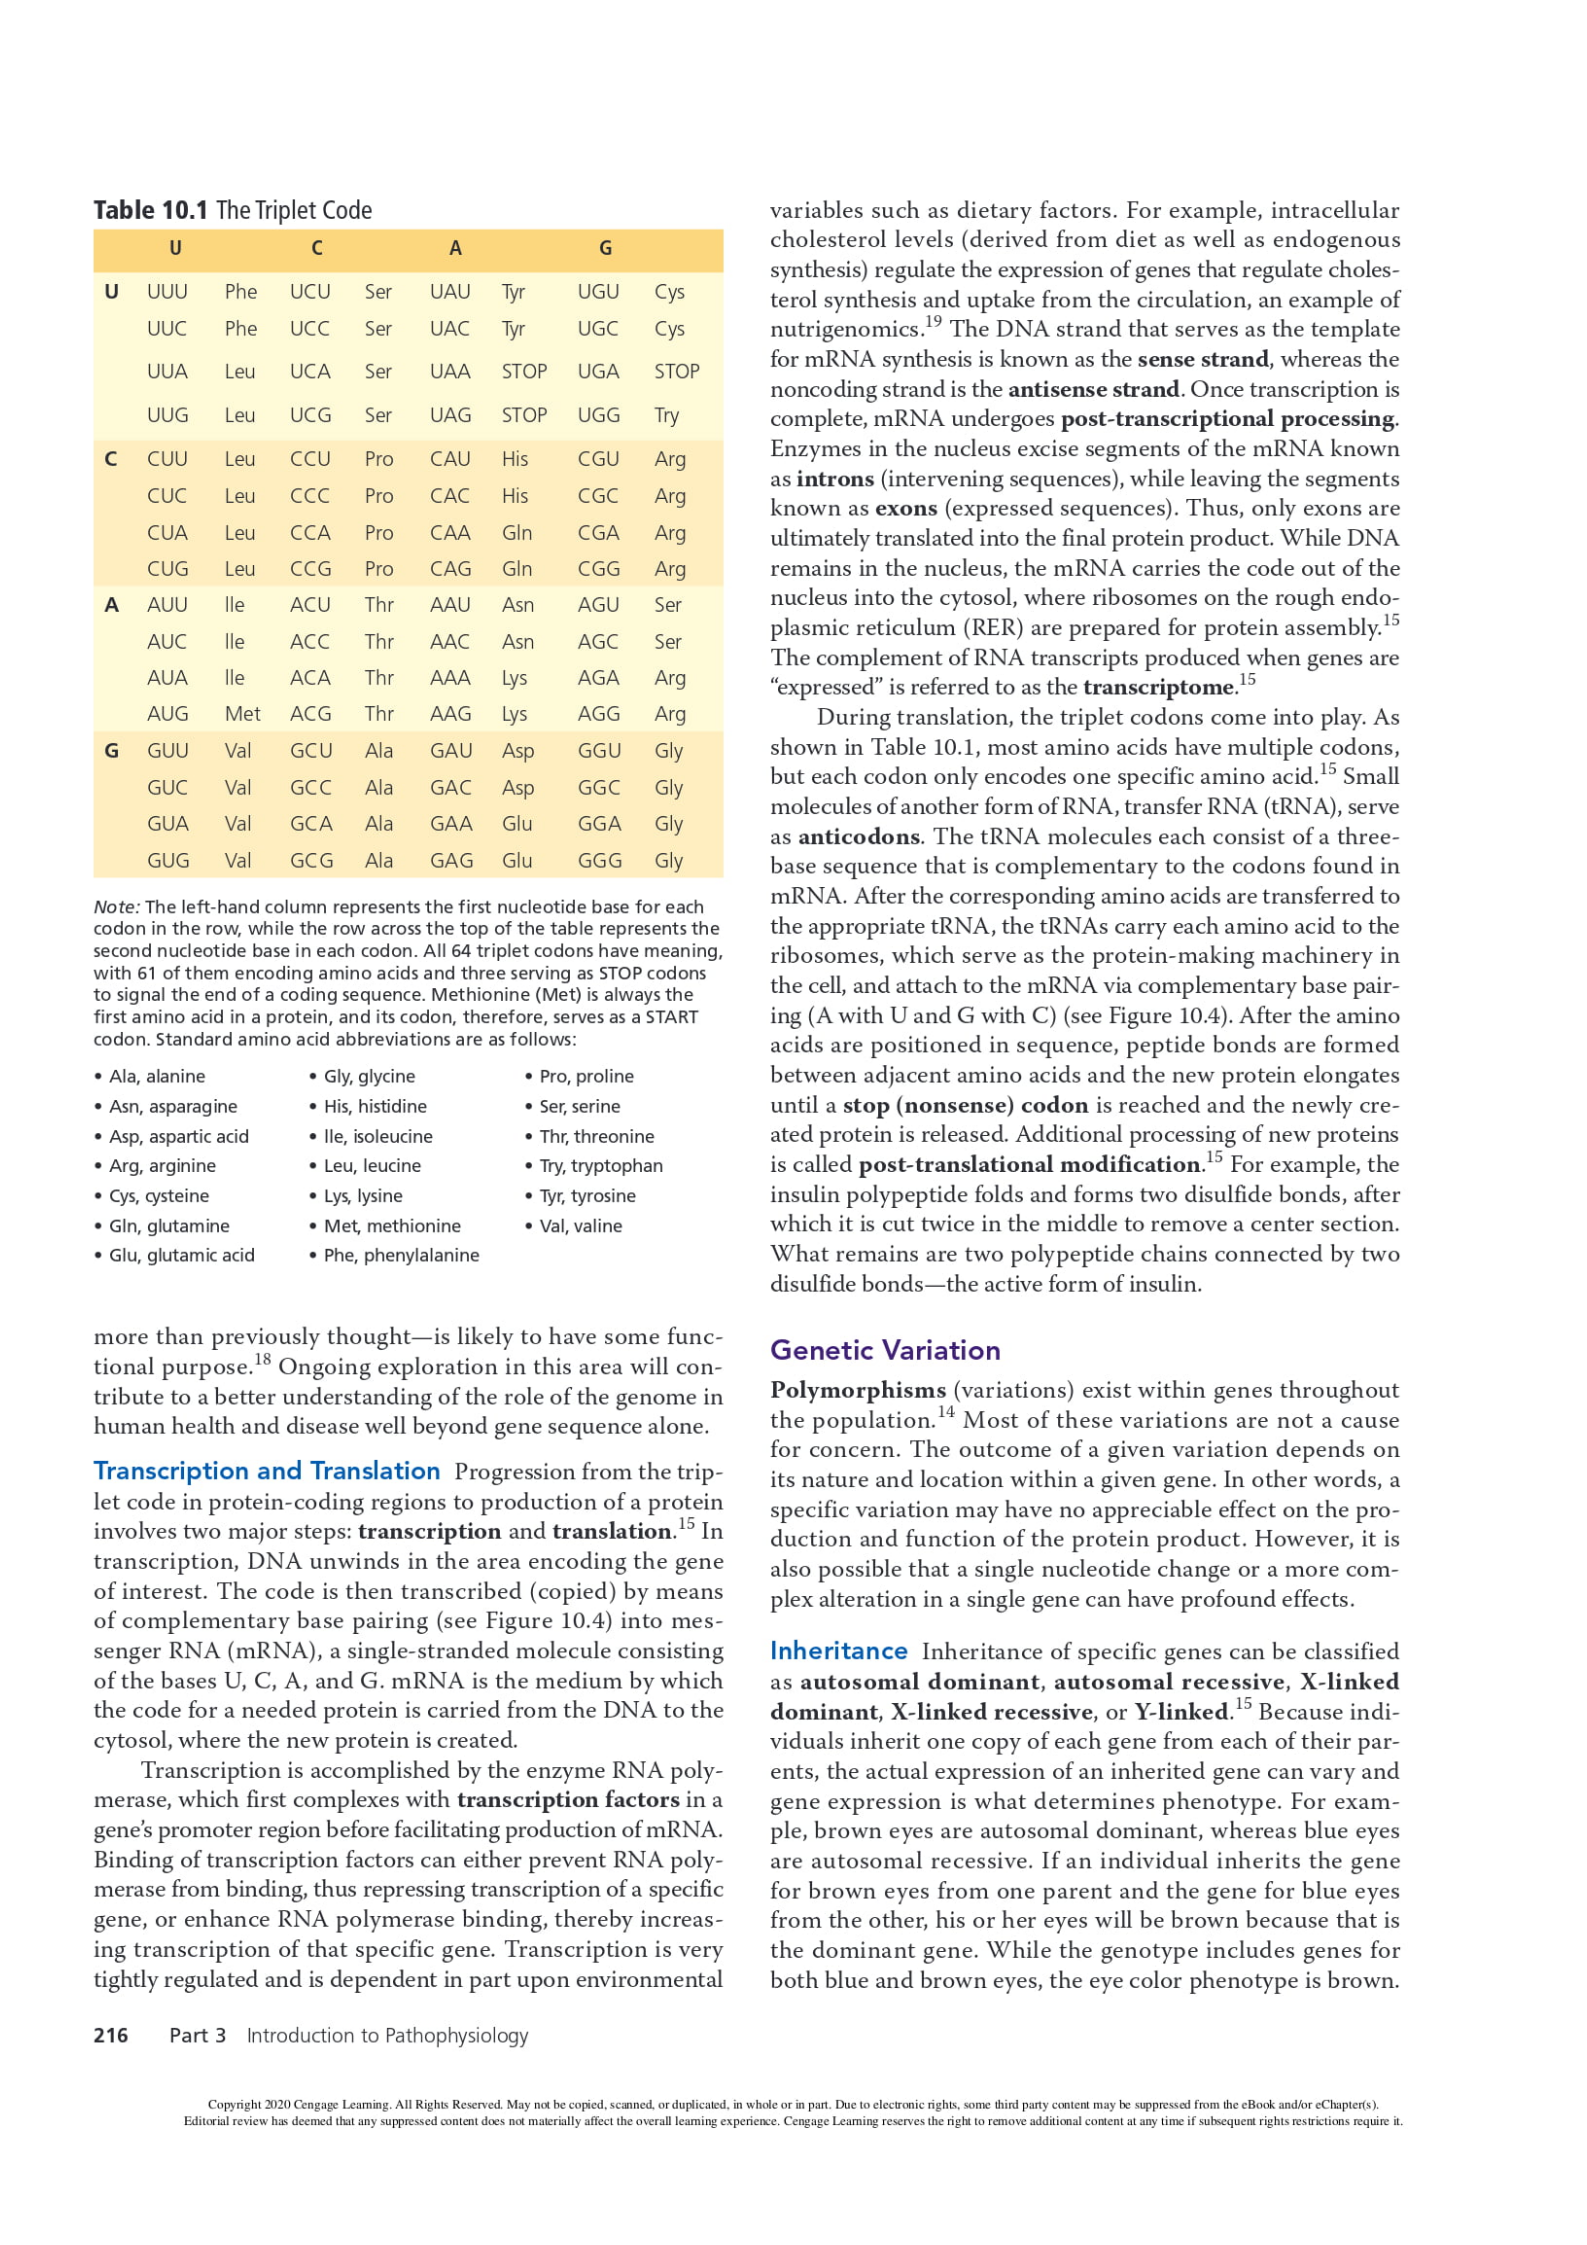
Table
10.1
The
Triplet
Code
U
UUU
Phe
UCU
Ser
UAU
Tyr
UGU
Cys
UUC
Phe
UCC
Ser
UAC
Tyr
UGC
Cys
UUA
Leu
UCA
Ser
UAA
STOP
UGA
STOP.
UUG
Leu
UCG
Ser
UAG
STOP
UGG
Try
Cc
CUU
Leu
CCU
Pro
CAU_
His
CGU
Arg
CUC
Leu
CCC
Pro
CAC
His
CGC
Arg
CUA
Leu
CCA
Pro
CAA
Gin
CGA
Arg
CUG
Leu
CCG
Pro
CAG
Gin
CGG
Arg
A
AUU
ile
ACU
Thr
AAU
Asn
AGU
Ser
AUC
lle
ACC
Thr
AAC
Asn
AGC
Ser
AUA
lle
ACA
Thr
AAA
Lys
AGA
Arg
AUG
Met
ACG
Thr
AAG
Lys
AGG
Arg
G
GUU_
Val
GCU
Ala
GAU_
Asp
GGU_
Gly
GUC
Val
Gcc
Ala
GAC
Asp
GGC
Gly
GUA
Val
GCA
Ala
GAA
Glu
GGA
Gly
GUG
Val
GCG
Ala
GAG
Glu
GGG
Gly
Note:
The
left-hand
column
represents
the
first
nucleotide
base
for
each
codon
in
the
row,
while
the
row
across
the
top
of
the
table
represents
the
second
nucleotide
base
in
each
codon.
All
64
triplet
codons
have
meaning,
with
61
of
them
encoding
amino
acids
and
three
serving
as
STOP
codons
to
signal
the
end
of
a
coding
sequence.
Methionine
(Met)
is
always
the
first
amino
acid
in
a
protein,
and
its
codon,
therefore,
serves
as a
START
codon.
Standard
amino
acid
abbreviations
are
as
follows:
*
Ala,
alanine
*
Gly,
glycine
*
His,
histidine
*
lle,
isoleucine
*
Pro,
proline
*
Asn,
asparagine
*
Ser,
serine
*
Asp,
aspartic
acid
*
Arg,
arginine
*
Thr,
threonine
*
Leu,
leucine
*
Try,
tryptophan
*
Cys,
cysteine
*
Lys,
lysine
©
Tyr,
tyrosine
*
Gin,
glutamine
*
Glu,
glutamic
acid
*
Met,
methionine
*
Phe,
phenylalanine
*
Val,
valine
more
than
previously
thought—is
likely
to
have
some
func-
tional
purpose.!®
Ongoing
exploration
in
this
area
will
con-
tribute
to
a
better
understanding
of
the
role
of the
genome
in
human
health
and
disease
well
beyond
gene sequence
alone.
Transcription
and
Translation
Progression
from
the
trip-
let
code
in
protein-coding
regions
to
production
of
a
protein
involves
two
major
steps:
transcription
and
translation.
In
transcription,
DNA
unwinds
in
the area
encoding
the
gene
of
interest.
The
code
is
then
transcribed
(copied)
by
means
of
complementary
base
pairing
(see
Figure
10.4)
into
mes-
senger
RNA
(mRNA),
a
single-stranded
molecule
consisting
of
the
bases
U, C,
A,
and
G.
mRNA
is
the
medium
by
which
the
code
for
a
needed
protein
is
carried
from
the
DNA
to
the
cytosol,
where
the
new
protein
is
created.
Transcription
is
accomplished
by
the
enzyme
RNA
poly-
merase,
which
first
complexes
with
transcription
factors
in a
gene's
promoter
region
before
facilitating
production
of
mRNA.
Binding
of
transcription
factors
can
either
prevent
RNA
poly-
merase
from
binding,
thus
repressing
transcription
of
a
specific
gene,
or
enhance
RNA
polymerase
binding,
thereby
increas-
ing
transcription
of
that
specific
gene.
Transcription
is
very
tightly
regulated
and
is
dependent
in
part
upon
environmental
216
Part
3
Introduction
to
Pathophysiology
variables
such
as
dietary
factors.
For
example,
intracellular
cholesterol
levels
(derived
from
diet
as
well
as
endogenous
synthesis)
regulate
the
expression
of
genes
that
regulate
choles-
terol
synthesis
and
uptake
from
the
circulation,
an
example
of
nutrigenomics.!?
The
DNA
strand
that
serves
as
the
template
for
mRNA
synthesis
is
known
as
the
sense
strand,
whereas
the
noncoding
strand
is
the
antisense
strand.
Once
transcription
is
complete,
mRNA
undergoes
post-transcriptional
processing.
Enzymes
in
the
nucleus
excise
segments
of
the
mRNA
known
as
introns
(intervening
sequences),
while
leaving
the
segments
known
as
exons
(expressed
sequences).
Thus,
only
exons
are
ultimately
translated
into
the
final
protein
product.
While
DNA
remains
in
the
nucleus,
the
mRNA
carries
the
code
out
of
the
nucleus
into
the
cytosol,
where
ribosomes
on
the
rough
endo-
plasmic
reticulum
(RER)
are
prepared
for
protein
assembly.!>
The
complement
of
RNA
transcripts
produced
when
genes
are
“expressed”
is
referred
to as
the
transcriptome.
During
translation,
the
triplet
codons
come
into
play.
As
shown
in
Table
10.1,
most amino
acids
have
multiple
codons,
but
each
codon
only
encodes
one
specific
amino
acid.!°
Small
molecules
of
another
form
of
RNA,
transfer
RNA
(tRNA),
serve
as
anticodons.
The
tRNA
molecules
each
consist
of
a
three-
base
sequence
that
is
complementary
to
the
codons
found
in
mRNA.
After
the
corresponding
amino
acids
are
transferred
to
the
appropriate
URNA,
the
(RNAs
carry
each
amino
acid
Lo
the
ribosomes,
which
serve
as
the
protein-making
machinery
in
the
cell,
and
attach
to
the
mRNA
via
complementary
base
pair-
ing
(A
with
U
and
G
with
C)
(see
Figure
10.4).
After
the
amino
acids
are
positioned
in
sequence,
peptide
bonds
are
formed
between
adjacent
amino
acids
and
the
new
protein
elongates
until
a
stop
(nonsense)
codon
is
reached
and
the
newly
cre-
ated
protein
is
released.
Additional
processing
of
new
proteins
is
called
post-translational
modification.!>
For
example,
the
insulin
polypeptide
folds
and
forms
two
disulfide
bonds,
after
which
it
is
cut
twice
in
the
middle
to
remove
a
center
section.
‘What
remains
are
two
polypeptide
chains
connected
by
two
disulfide
bonds—the
active
form
of
insulin.
Genetic
Variation
Polymorphisms
(variations)
exist
within
genes
throughout
the
population.'*
Most
of
these
variations
are
not
a
cause
for
concern.
The
outcome
of
a
given
variation
depends
on
its
nature
and
location
within
a
given
gene.
In
other
words,
a
specific
variation
may
have
no
appreciable
effect
on
the
pro-
duction
and
function
of the
protein
product.
However,
it
is
also
possible
that
a single
nucleotide
change
or
a
more
com-
plex
alteration in a
single
gene
can
have
profound
effects.
Inheritance
Inheritance
of
specific
genes
can
be
classified
as
autosomal
dominant,
autosomal
recessive,
X-linked
dominant,
X-linked
recessive, or
Y-linked.!°
Because
indi-
viduals
inherit
one
copy
of
each
gene
from
each
of
their
par-
ents,
the
actual
expression
of
an
inherited
gene
can
vary
and
gene
expression
is
what
determines
phenotype.
For
exam-
ple,
brown
eyes
are
autosomal
dominant,
whereas
blue eyes
are
autosomal
recessive.
If
an
individual
inherits
the
gene
for
brown
eyes
from
one
parent
and
the
gene
for
blue eyes
from
the
other,
his
or
her
eyes
will
be
brown
because
that
is
the
dominant
gene.
While
the
genotype
includes
genes
for
both
blue
and
brown
eyes,
the
eye
color
phenotype
is
brown.
Copyright
2020
Cengage
Leaming.
All
Rights
Reserved.
May
not
be
copied,
scanned,
or
duplicated,
in
whole
or
in
part.
Due
to
electronic
rights,
some
third
party
content
may
be
suppressed
from
the
eBook
and/or
eChapter(s).
Editorial
review
has
deemed
that
any
suppressed
content
does
not
materially
affect
the
overall
leaming
experience,
Cengage
Learning
reserves
the
right
to
remove
additional
content
at
any
time
if
subsequent
rights
restrictions
requice
i
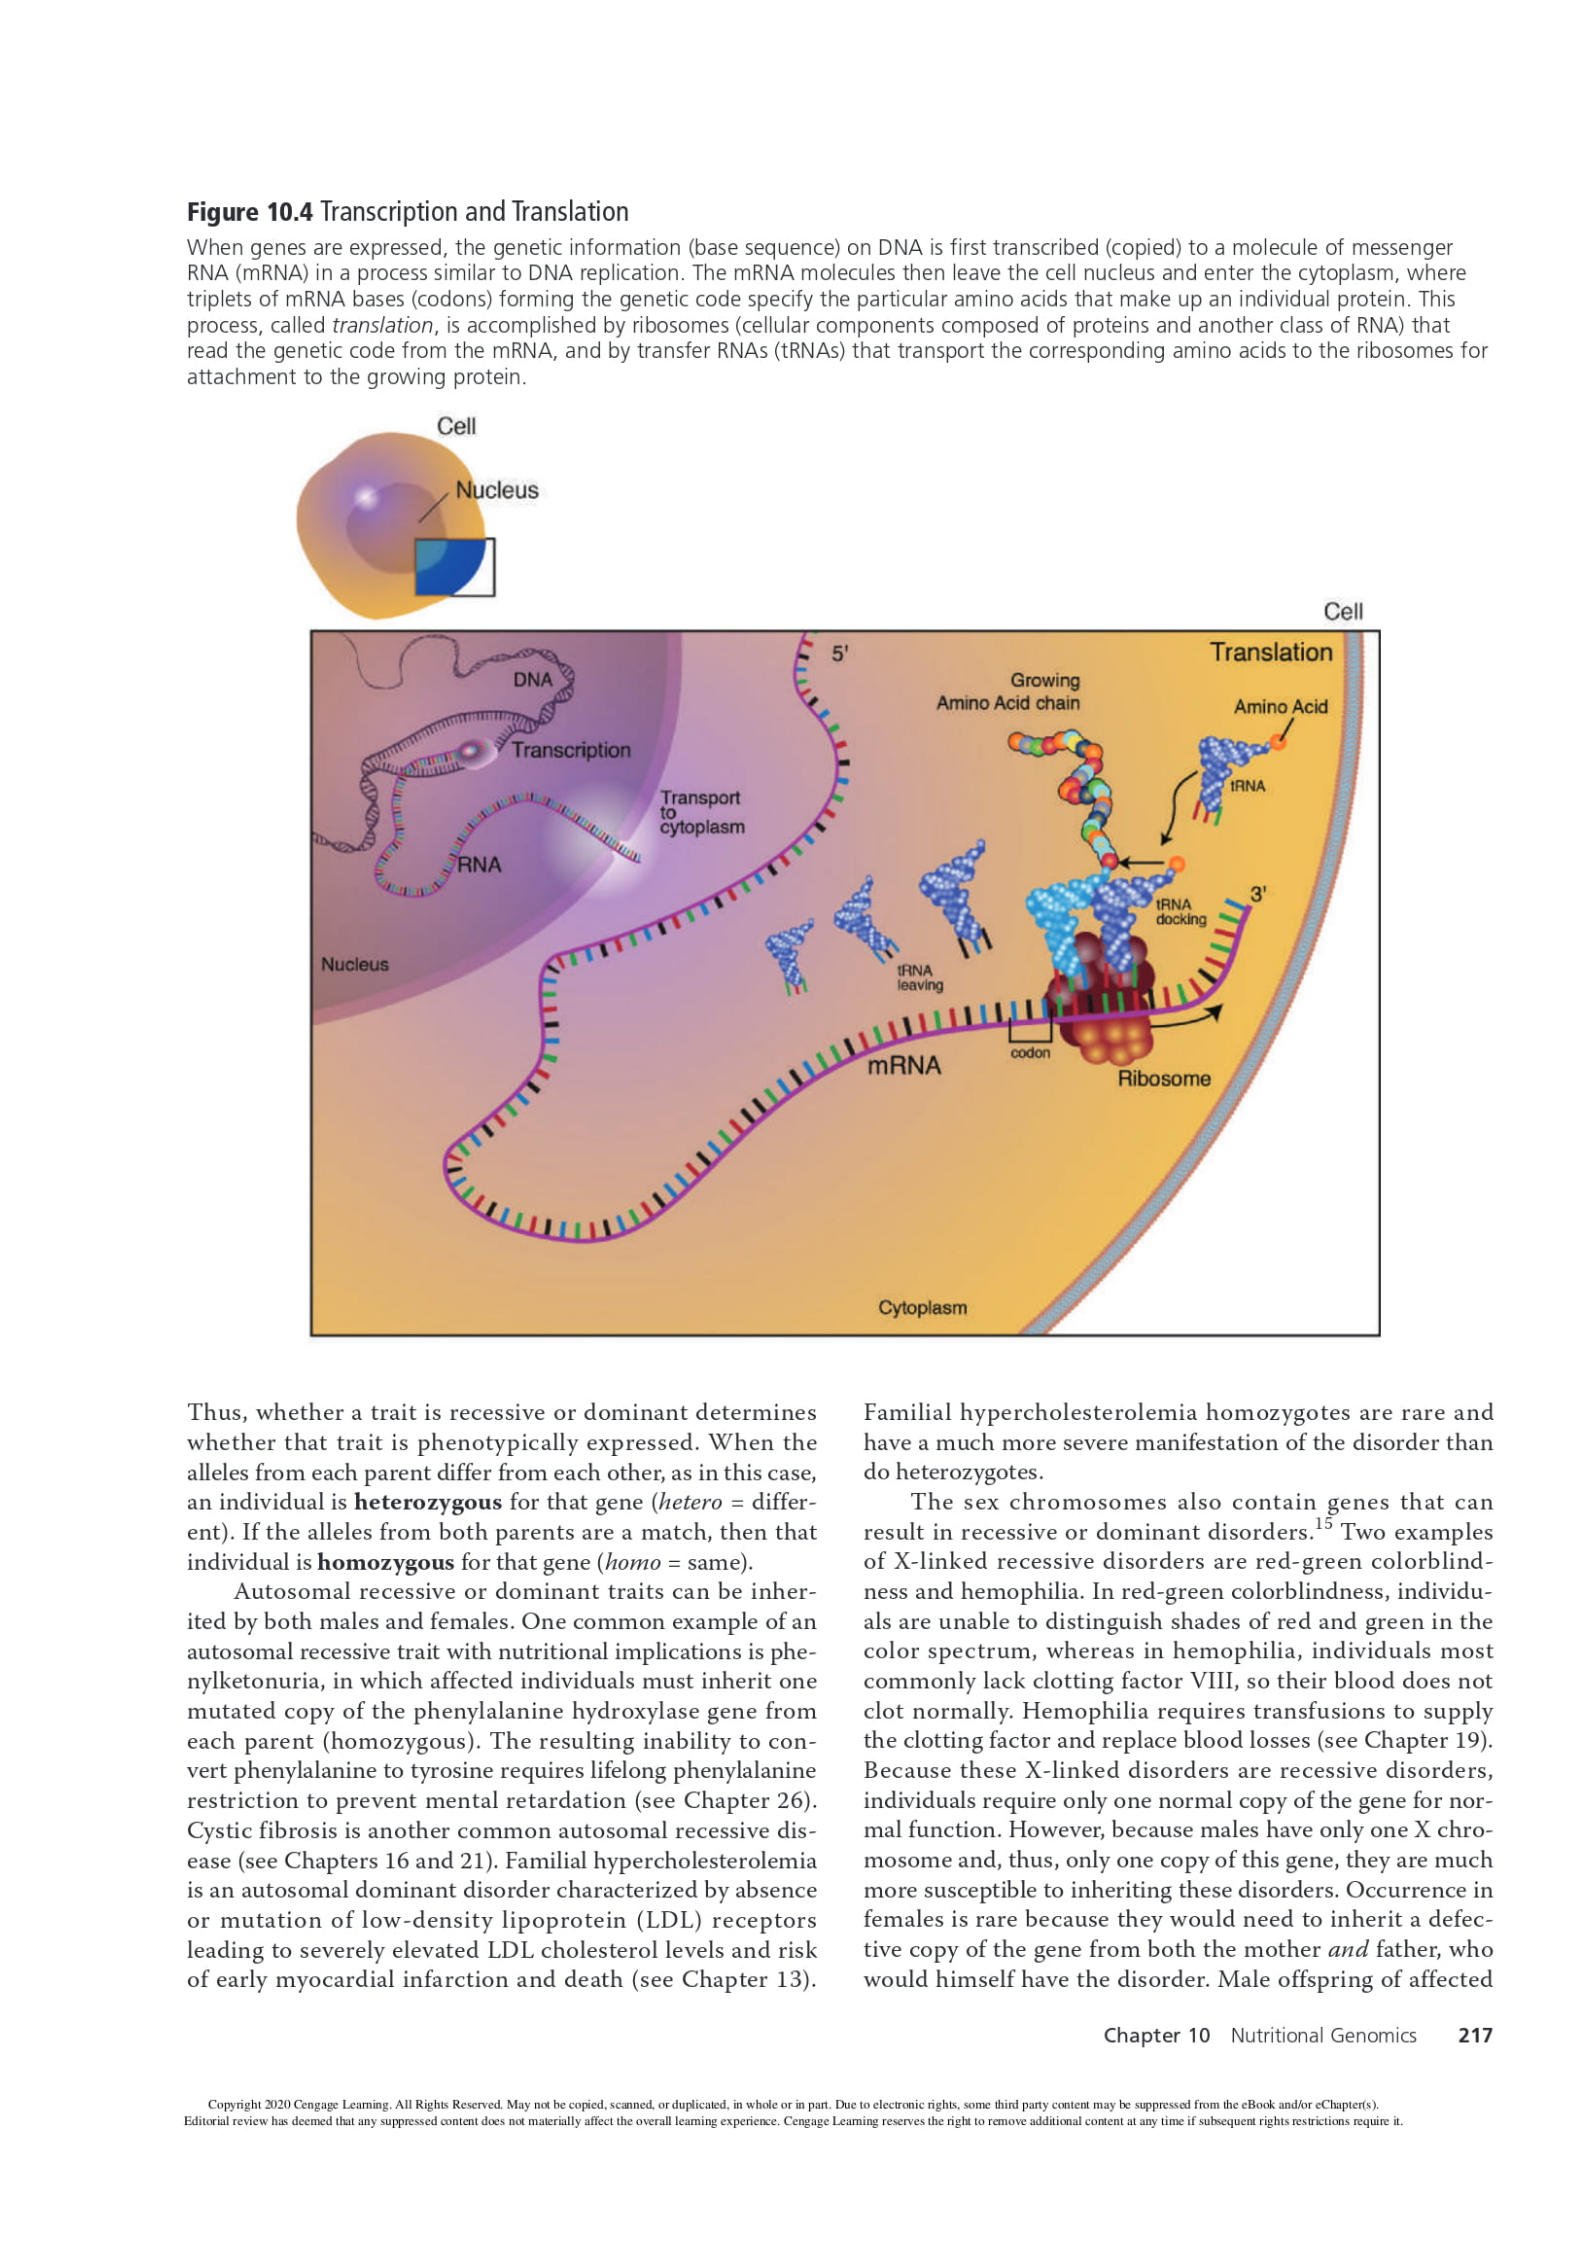
Figure
10.4
Transcription
and
Translation
When
genes
are
expressed,
the
genetic
information
(base
sequence)
on
DNA
is
first
transcribed
(copied)
to
a
molecule
of
messenger
RNA
(mRNA)
in
a
process
similar
to
DNA
replication.
The
mRNA
molecules
then
leave
the
cell
nucleus
and
enter
the
cytoplasm,
where
triplets
of
mRNA
bases
(codons)
forming
tne
genetic
code
specify
the
particular
amino
acids
that
make
upan
individual
protein.
This
process,
called
translation,
is
accomplished
by
ribosomes
(cellular
components
composed
of
proteins
and
another
class
of
RNA)
that
read
the
genetic
code
from
the
mRNA,
and
by
transfer
RNAs
(tRNAs)
that
transport
the
corresponding
amino
acids
to
the
ribosomes
for
attachment
to
the
growing
protein.
Cell
Thus,
whether
a
trait
is
recessive
or
dominant
determines
whether
thattrait
is
phenotypically
expressed.
When
the
alleles
from
each
parent
differ
from
each
other,
as
in
this
case,
an
individual
is
heterozygous
for
that
gene
(/etero
=
differ-
ent).
If
the
alleles
from
both
parents
are
a
match,
then
that
individual
is
homozygous
for
that
gene
(homo
= same).
Autosomal
recessive
or
dominant
traits
can
be
inher-
ited
by
both males
and
females.
One
common
example
of
an
autosomal
recessive
trait
with
nutritional
implications
is
phe-
nylketonuria,
in
which
affected
individuals
must
inherit
one
mutated
copy
of
the
phenylalanine
hydroxylase
gene
from
each
parent
(homozygous).
The
resulting
inability
to
con-
vert
phenylalanine
to
tyrosine requires
lifelong
phenylalanine
restriction
to
prevent
mental
retardation
(see
Chapter
26).
Cystic
fibrosis
is
another
common
autosomal
recessive
dis-
ease
(see
Chapters
16
and
21).
Familial
hypercholesterolemia
is
an
autosomal
dominant
disorder
characterized
by
absence
or
mutation
of
low-density
lipoprotein
(LDL)
receptors
leading
to
severely
elevated
LDL
cholesterol
levels
and
risk
of
early
myocardial
infarction
and
death
(see
Chapter
13).
Cell
Familial
hypercholesterolemia
homozygotes
are rare
and
have
a
much
more
severe
manifestation
of
the disorder
than
do
heterozygotes.
The
sex
chromosomes
also
contain
genes
that
can
result
in
recessive
or
dominant
disorders.!°
Two
examples
of
X-linked
recessive
disorders
are
red-green
colorblind-
ness
and
hemophilia.
In
red-green
colorblindness,
individu-
als
are
unable
to
distinguish
shades
of
red
and
green
in
the
color
spectrum,
whereas
in
hemophilia,
individuals
most
commonly
lack
clotting
factor
VIII,
so
their
blood
does
not
clot
normally.
Hemophilia
requires
transfusions
to
supply
the
clotting
factor
and
replace
blood
losses
(see
Chapter
19).
Because
these
X-linked
disorders
are recessive disorders,
individuals
require
only
one
normal
copy
of
the
gene
for
nor-
mal
function.
However,
because
males
have
only
one
X
chro-
mosome
and,
thus,
only
one
copy
of
this
gene,
they
are
much
more
susceptible
to
inheriting
these
disorders.
Occurrence
in
females
is
rare
because
they
would
need
to
inherit
a
defec-
tive
copy
of
the
gene
from
both
the
mother
and
father,
who
would
himself
have
the
disorder.
Male
offspring
of
affected
Chapter
10
Nutritional
Genomics.
217
Copyright
2020
Cengage
Leaming.
All
Rights
Reserved.
May
not
be
copied,
scanned,
or
duplicated,
in
whole
or
in
part.
Due
to
electronic
rights,
some
third
party
content
may
be
suppressed
from
the
eBook
and/or
eChapter(s).
Editorial
review
has
deemed
that
any
suppressed
content
does
not
materially
affect
the
overall
learning
experience.
Cengage
Learning
reserves
the
right
toremove
additional
content
at
any
time
if
subsequent
rights
restrictions
requize
it,

fathers
will
not
inherit
the
disorder
because
only
a
Y
chro-
mosome
is
inherited
from
the
father.
However,
female
off-
spring
of
affected
fathers
are
carriers
(heterozygotes),
and
male
children
born
to
them
have
a
50%
chance
of
having
the
disorder,
depending
wholly
on
which
copy
of
the
maternal
X
chromosome
is
passed
on.
X-linked
dominant
traits
are
rel-
atively
rare.
Y-linked
disorders
are
extremely
rare,
occurring
only
in
males
as
a
result
of
the
inheritance
of
mutations
in
the
Y
chromosome
from
the
father.
Y-linked
disorders
are
not
considered
dominant
or
recessive
because
only
one
copy
of
the
affected
chromosome
can
exist
in
an
individual.
Single-Nucleotide
Polymorphisms
Understand-
ing
monogenic
disorders
such
as
those
described
earlier
helps
lay
the
groundwork
for
comprehending
the
complex-
ities
of
polygenic
diseases
such
as
obesity,
diabetes,
cancer,
and
CVD.
The
study
of
gene—nutrient
interactions
that
are
dependent
upon
gene
variance
(nutrigenetics)
is
focused
pri-
marily
on
single-nucleotide
polymorphisms
(SNPs;
pro-
nounced
“snips”).?
SNPs
are
defined
as
those
genetic
variants
or
polymorphisms
in
which
a
single
nucleotide
is
present
in
place
of
another.
For
example,
in
place
of the
more
common
codon
UGU,
the
codon
UGC
is
found.
Because
both
encode
the
amino
acid
cytosine,
this
particular
SNP
does
not
result
in
any
difference
in
function.
However,
if
UGA
is
present
in
place
of
UGU,
that
is
a
potential
problem,
because
UGA
is
a
nonsense
orstop
codon
(see
example
of
a
SNP
in
Figure
10.5).
Depending
on
the
location
of the
polymorphism
within
a
gene,
there
could
be
deleterious
effects.
If
the
affected
codon
is
near
the
end
of
a
coding
sequence,
it
is
possible
that
the
Figure
10.5
DNA
Sequence
Variation
in
a
Gene
Specific
codons
direct
the
cell's
protein-synthesizing
machinery
to
add
specific
amino
acids.
For
example,
the
base
sequence
ATG
codes
for
the
amino
acid
methionine.
Since three
bases
code
for
one
amino
acid,
the
protein
coded
by an
average-sized
gene
(3000
bp)
will
contain
1000
amino
acids.
The
DNA
code
is
thus
a
series
of
codons
that
specify
which
amino
acids
are
required
to
make
up
specific
proteins.
Some
variations
in
a
person’s
genetic
code
will
have
no
effect
on
the
protein
that
is
produced;
others
can
lead
to
disease
or
an
increased
susceptibility
to
disease.
DNA
Sequence
Variation
in
a
Gene
Can
Change
the
Protein
Produced
by
the
Genetic
Code
GCA AGA
GAT
AAT
TCT...
final
protein
product
will
not
be
functionally
altered.
How-
ever,
if
UGG
is
present
rather
than
UGU,
then
altering
that
one
amino
acid
from
cytosine
to
tryptophan
has
the
potential
for
altering
the
shape
and
function
of
the
protein
product.
SNP
nomenclature
standardization
has
been
evolving,
but
various
examples
appear
throughout
the
research
litera-
ture.
SNPs
may
include
a
SNP
ID
and
are
generally
identified
also
by
the
gene
name,
the
location
of
the
affected
nucleotide
within
the
gene
sequence,
the
common
nucleotide
in
that
position,
and
an
arrow
indicating
that
a
less
common
nucle-
otide
is
present.
For
example,
MTHFR
677C>T
indicates
that
there
is
a
SNP
at
nucleotide
number
677
in
one
allele
of
the
methylenetetrahydrofolate
(MTHFR)
reductase
gene
charac-
terized
by
a
thymine
in
place
of
the
more
common
cytosine.
Since
each
individual
inherits
one
copy
of
the
gene
from
each
parent,
genotype
can
further
identify
them
as
MTHFR
677CC,
677
CT,
or
677TT
to
indicate
the
nucleotides
in
place
at
posi-
tion
677
in
both
copies
of
the
gene.
The
MTHFR
677C>T
SNP
results
in
an
amino
acid
change
in
that
position
from
the
typical
alanine
to
the
less
typical
valine.
This
particular
SNP
has
implications
for
folate
metabolism
and
cancer
risk,
as dis-
cussed
later
in
this
chapter.
SNPs
may
also
be
defined
by
the
amino
acid
change;
for
instance,
PPARA-Leul62Val
indicates
the
162nd
amino
acid
in
the
protein
sequence
for
peroxisome
proliferator
activated
receptor-a
is
a
valine
(Val)
when
the
typical
amino
acid
in
this
position
is
a
leucine
(Leu).
Other
similar
variations
may
be
seen
in
the
literature
as
well.
Note
that
symbols
for
genes
are
commonly
italicized,
whereas
ref-
erences
to
their
protein
products
are
not,
although
alternative
nomenclature
for
genes
is
prevalent
in
the
literature.
Identification
of
SNPs
has
been
a
primary
focus
of
genomics
research
since
completion
of
the
Human
Genome
Project
in
2003.
The
human
genome
has
approximately
10
million
polymorphisms,
meaning
that
any
two
unrelated
humans
have
millions
of
genetic
differences.”
These
poly-
morphisms
are
not
all
independent
of
each
other.
Rather,
when
specific
gene
variant
is
present
on
a
chromo-
some,
it
is
associated
with
other
par-
ticular
gene
variants
on
that
same
chromosome.
This
group
of
gene
variants
that
associate
together
is
referred
to
as a
haplotype,
and
these
Protein
Products
variants
may
work
in
concert
to
pro-
Gene
A
from
Person
1 on
1
2 3
4
5
Gene
A
from
GCG
AGA
GAT AAT
TCT...
Person2
Codon
change
made
no
difference
in
amino
acid
sequence
1
2
3
4
5
GCA
AAA
Codon
change
resulted
in
Ea
[re]
a
difference
in
amino
acid
at
position
2
1
2
GAT
AAT
TCT
...
3
4
5
Gene
A
from
Person
3
Source:
U.S.
Department
of
Energy
Human
Genome
Program,
http://genomics.energy.gov.
218
Part
3
Introduction
to
Pathophysiology
duce
a
specific
phenotype.
One
focus
in
genomics
research
now
is
to
deter-
mine
which
of
these
millions of
poly-
morphisms
is
likely
to
be
functionally
important,
and
to
continue
to
identify
how
each
might
relate
to
each
other
and
to
environment
and
health.”!
Other
Polymorphisms
Other
types
of
polymorphisms
include
insertion
or
deletion
polymor-
phisms,
in
which
a
number
of
nucle-
otide
base
pairs
are
either
added
to
or deleted
from
a
gene.
For
example,
Copyright
2020
Cengage
Leaming.
All
Rights
Reserved.
May
not
be
copied,
scanned,
or
duplicated,
in
whole
or
in
part.
Due
to
electronic
rights,
some
third
party
content
may
be
suppressed
from
the
eBook
and/or
eChapter(s).
Editorial
review
has
deemed
that
any
suppressed
content
does
not
materially
affect
the
overall
leaming
experience.
Cengage
Learning
reserves
the
right
to
remove
additional
content
at
any
time
if
subsequent
rights
restrictions
requice
i

the
angiotensin-converting
enzyme
(ACE)
gene
has
an
inser-
tion/deletion
polymorphism
characterized
by
the
presence
or
absence
of
a
287—base
pair
fragment
in
one
of
its
introns,
which
is
linked
to
alterations
in
circulating
levels
of
ACE
and
risk
of
renal
complications
related
to
type
2
diabetes.””
Frameshift
mutations
can occur
when
the
reading
frame
of
a gene
is
altered
by
inserting
or
deleting
a
single
nucleotide
or
series
of
nucleotides.
These
tend
to
have
less
impact
if
the
insertion
is
in
the
form
of
a
triplet
but
can
be
devastating
when
only
one
or
two
nucleotides
are
inserted.
For
example,
see
what
happens
when
the
reading
frame
for
the
following
sequence
is
shifted
by
an
insertion
of
a
single
nucleotide
(ade-
nine,
shown
in
red):
.
CUU
AUG UUA
CGU
AAG...
Leu
Met
Leu
Arg Lys
.
CUU AAU
GUU
ACG
UAA
4G...
Leu
Asn
Val
Thr
STOP
Other
syndromes
can
occur
as
result
of
inheriting
extra
copies of
chromosomes,
as in
Down
syndrome,
or
deletions
of sections of
chromosomes,
which
is
one
cause
of
the
neuro-
logical
disorder
Angelman
syndrome.
Epigenetic Regulation
Epigenetics
relates
not
to
the
genome
sequence
itself
but
to
the inherited
pattern
of
gene
expression
regulated
by
modifi-
cations
to
DNA.°
Gene
expression
is
regulated
in
many
ways,
including
DNA
methylation;
histone
methylation,
acetyla-
tion,
or
phosphorylation;
and
transcription
factors.!®
More
recently,
noncoding
RNAs,
such
as
the
miRNAs
described
earlier
in
the
chapter,
have
been
identified
as
playing
a
reg-
ulatory
role
as
well.!””>
All
these regulatory
mechanisms
can
be
influenced
by
early
programming
in
response
to
nutrition
and
other
environmental
factors
in
fetal
life
or infancy
as
well
as
throughout
the
life
span.
For
example,
monozygotic
(iden-
tical)
twins
have
an
identical
genotype
but
have
been
found
to
have
differing
epigenetic
patterns
as
they
got
older.2*”>
This
was
especially
true of
those
who
spent
more
of
their
lifetime
apart
and
had
the
greatest
lifestyle
differences.
This
could
explain
differences
in
disease
risk
in
twin
pairs
and
indicates
that
modifying
the
epigenome
to
activate
or
suppress
genes
through
diet
has
potential
to
modify
risk
of
chronic
disease
and
cancer.
Epigenetic
patterns
may
also
be
passed
from
one
generation
to
the
next;”°
thus,
individual
patterns
may
reflect
environmental
exposures
of
previous
generations.
DNA
Methylation
Although
humans
have
the
full
comple-
ment
of
genetic
material
in
all
nucleated
cells, not
all
genes
are
expressed
in
all
cells,
and
the
actual
level
of
expression
var-
ies
based
on
DNA
methylation
patterns.
Each
tissue
type
in
the
body
has
a
distinctive
methylation
pattern
that
results
in
the
tissue-specific
gene
expression,’
such
as
the
expression
of the
gene
for
insulin
only
in
the
beta
cells
of the pancreas.
Approximately
2%-5%
of
cytosines
in
mammalian
DNA
are
methylated,
primarily
in
CpG
dinucleotides
present
in
the
promoter
regions
of
genes,
and
the pattern
of
methylation
is
inherited,
though
it
also
changes
with
aging
and
is
influenced
by
environmental
factors.!°
This
methylation
(a
CH;
group
is
donated
by
S-adenosylmethionine
or
SAM)
provides
tight
con-
trol
over
genes
by
keeping
chromatin
(DNA
plus
the
histone
proteins
with
which
it
is
associated)
condensed
and
thereby
suppressing
gene
expression,
or
keeping
the
genes
“silenced?!
For
most
genes,
both
maternal
and
paternal
alleles
con-
tribute
to
production
of the
protein
product,
but
for
others,
genomic
imprinting
takes
place.
In
other
words,
for
specific
genes,
only
the
maternal
or
paternal
allele
is
expressed.
For
example,
the
gene
encoding
insulin-like
growth
factor
2
(IGF2)
is
expressed
only
from
the
paternal
allele,
while
the
maternal
allele
in
mammals
is
silenced.2”
In
humans,
it
is
predicted
that
there
are
a
few
hundred
imprinted
genes.”*
Imprinting
errors
can
result
in
devastating
outcomes
in
offspring,
including
the
neurological disorders
Angelman
syndrome
and
Prader—Willi
syndrome.”
It
is
proposed
that
imprinted
genes
(as
opposed
to
gene
sequence)
hold
the
most
promise
for
rapid evolution-
ary
adaptation
to
changes
in
the
nutritional
environment
and
may
therefore
be
implicated
in
the
current
epidemic
of
obe-
sity,
metabolic
syndrome,
and
type
2
diabetes mellitus.”
Methyl
groups
are
derived
from
dietary
sources
including
folate,
choline,
methionine,
and
vitamin
By.”
As
shown
in
Figure
10.6,
MTHER
catalyzes
conversion
of
5,10-methylenetetrahydrofolate
to
5-methyl-tetrahydrofolate,
which
then
donates
ils
methyl
group
Lo
vitamin
Bj).
Vitamin
By,
thus
activated,
then
methylates
homocysteine
in
order
to
form
methionine.
Alternatively,
choline
can
be
converted
to betaine,
which
can
also
methylate
homocysteine
to
form
methionine.
Methionine
adenosyl
transferase
then
unites
methionine
with
adenosine
to
form
SAM,
which
methylates
DNA
via
the
action of
DNA
methyltransferases.°°
Thus,
dietary
adequacy
plays
a
role in
maintaining
appropriate
DNA
methylation.”
A
deficiency
of
methyl
groups
related
to lack
of the
previously
listed
nutrients
means
that
as
cells
divide,
methylation
may
be
reduced,
and
some
of
that
tran-
scriptional
regulation
is
lost.
Impaired
methylation
of
DNA
is
related
strongly
to
impaired
fetal
development
and
can-
cer?!
For
example,
hypomethylation
of
DNA
is
related
to
chromosomal
instability,
including
gain
or
loss
of
entire
chro-
mosomes
or
increased
gene
mutation
rates
during
mitosis,
both
of
which
can
contribute
to
cancer.*”
Research
also
sug-
gests
that
hypomethylation
of
DNA
coupled
with
genetic
risk
factors
contributes
to
greater
susceptibility
to
autoimmune
diseases
such
as
type
1
diabetes
mellitus.*”
Histone
Modification
Like
DNA
methylation,
histone
modification
is
a
form
of
epigenetic
regulation.**
Histones
are
small
proteins
around
which
DNA
is
wrapped.
The
histone
tail
can be
modified
by
methylation,
acetylation,
phosphoryla-
tion,
ubiquitination,
biotinylation,
and
so
forth,
which
helps
to
regulate
transcription,
DNA
repair,
apoptosis
(programmed
cell
death),
mitosis,
and
meiosis.
This
pattern
is
often
referred
to
as
the
histone
code.
Histone
modifications
work
in
concert
with
DNA
methylation
to
determine
shape
and
accessibility
of
chromatin
for
transcription
(see
Figure
10.7).
For
example,
enzymes
called
histone
acetyltransferases
attach
acetyl
groups
to
histones,
and
this
acetylation
is
associated
with
unfolding
and
accessibility
of
chromatin
for
transcription,
whereas
his-
tone
deacetylases,
which
remove
acetyl
groups,
promote
fold-
ing
of
chromatin
and
block
gene
transcription.
Several
dietary
factors—including
sulforaphane
in
cruciferous
vegetables,
Chapter
10
Nutritional
Genomics.
219
Copyright
2020
Cengage
Leaming.
All
Rights
Reserved.
May
not
be
copied,
scanned,
or
duplicated,
in
whole
or
in
part.
Due
to
electronic
rights,
some
third
party
content
may
be
suppressed
from
the
eBook
and/or
eChapter(s).
Editorial
review
has
deemed
that
any
suppressed
content
does
not
materially
affect
the
overall
leaming
experience.
Cengage
Learning
reserves
the
right
to
remove
additional
content
at
any
time
if
subsequent
rights
restrictions
requice
i

pH
The
unit
for
measuring
relative
acidity
or
alkalinity
of
a
fluid
is
called
pH.
Simply
stated,
pH
is
the
ratio
of
acids
to
bases.
Hydrogen
ion
concentration
(H*)
is
the
negative
logarithm
of
hydrogen
ions
in
solution:
pH
=
log
1/[H*]
=
—log[H*]
Because
the
scale
of
H*
is
logarithmic,
in
order
for
the
pH
to
change
by
one
unit
(e.g.,
changing
from
to
4),
there
must
be
a
10-fold
change
in
H*.
The
pH
of
a
substance
is
measured
in
a
range
from
1
to
14.
A
1
on
the
pH
scale
indicates
the
most
acidic,
anda
14
indi-
cates
the
most
alkaline.
Water
is
considered
neutral
at
7.0.
For
humans,
a
normal
serum
pH
is
within
the
range
of
7.35—7.45.
Note
that
reported
normal
values
for
arterial
pH
vary
among
the
numerous
references
available;
for
this
chapter,
the
range
of
7.35—7.45
is
used.!~?
As
shown
in
Figure
8.1,
the
pH
of
other
body
fluids
varies,
with
gastric
juice
being
the
most
acidic.
Terms
Describing
pH
Acidosis
is
the
process
(or
processes)
that
leads
to
accumu-
lation
of acid or
loss
of
base.
Acidemia
is
the
actual
decrease
in
pH
within
the
body
to <7.35.
Likewise,
alkalosis
is
the
process
(or
processes)
that
leads
to
accumulation
of
base
or
loss
of
acid,
whereas
alkalemia
is
the
condition
where
an
actual
increase
of
pH
>7.45
is
observed.
In
clinical
practice,
this
distinction
is
generally
not
made
and
the
terms
acidosis
and
alkalosis
are
used
to
refer
to
abnormal
pH.
8.3
REGULATION
OF
ACID-BASE
BALANCE
As
illustrated
in
Figure
8.2,
the
body
has
several
physiological
means
of
accommodating
all
the
hydrogen
ions
it
constantly
produces.
These
include
(1)
chemical
buffers,
(2)
the
respi-
ratory
regulation
of
pH,
and
(3)
the
kidney
regulation
of
pH.
Chemical
Buffering
A
buffer
reacts
with
free
H*
in
order
to
maintain
acid-base
equilibrium.
Effectiveness
or
the
power
of
the
particular
buf-
fer
is
determined
by
its
association
with
cellular
salt
(pK)
and
by
its
overall
concentration
in
the
fluid
compartment.
Buffers
are
present
in
all
body
fluids—both
extracellular
and
intracellular.
Table
8.1
summarizes
the
chemical
buffers.
The
Bicarbonate-Carbonic
Acid
Buffer
System
The
primary
buffer
in
extracellular
fluid
(ECF)
is
the
bicarbonate—
carbonic
acid
buffer
system.
This
buffer
system
accommo-
dates
more
than
80%
of
the
required
buffering
in
the
ECF.
It is
outlined
as
follows:
H*
+
HCO,
+
H,CO,
4
CO,
+
H,O
As
the
buffer
system
reacts
with
fixed
acids,
HCO;
is
produced.
As
discussed
previously,
HyCO3
readily
dissolves
to
CO,
and
H,O.
Therefore,
the
lungs
will
accommodate
the
increased
load
of
acids
by
increasing
rate
and
depth
of
breath-
ing
and by
expiring
the
CO,
(see
Figure
8.2).
The
kidney
Figure
8.1
pH
of
Body
Fluids
and
Other
Common
Solutions
pH
Hydrochloric
acid
(HCl)
Gastric
fluid
(1.0-3.0)
Lemon
juice,
cola
drinks,
we
bd
some
acid
rain
Vinegar,
wine,
beer,
oranges
Acidic
*
es
®
&
Tomatoes
Bananas
Black
coffee
_
Bread
Typical
rainwater
2
6
Urine
(5.0-70)
il
!
Milk
(6.6)
ll
pa
7
Pure
water
[H*]
=
[OH7]
Blood
(735-745)
Ka
Egg
white
(8.0)
we
Seawater
(7.8-8.3)
Baking
soda
Phosphate
detergents,
bleach,
antacids
Soapy
solutions,
.
milk
of
magnesia
Basic
ses
Household
ammonia
(10.5—-11.9)
Hair
remover
Oven
cleaner
Sodium
hydroxide
(NaOH)
helps
with
this
buffer
system
by
either
reabsorbing
HCO3"
or
regenerating
additional
HCO;
from
CO,
and
H,0.!”
Historically,
the
Henderson—Hasselbalch
equation
has
been
used
to
explain
the
interrelationships
between
HCO,
HCO,
,,
and
pH.
In
humans,
the
pH,
or
ratio
of
acids
to bases,
is
1
part
HyCO3
to
20
parts
HCO;
.
In
order
for
pH
to
remain
within
the
normal
range,
this
ratio
has
to
be
maintained.
Any
change
in
HyCO3
must
be
accompanied
by
a
proportional
change
in
HCO,g
..
If
one
part of the
equation
changes
without
the
other
and
the
ratio
is
not
maintained,
pH
will
move
out
of
the
normal
range.
Other
Chemical
Buffer
Systems
The
body
has
additional
buffer
systems
in
place
to
compensate
for
changes
that
could
occur
from
other
sources
of
acid.
An
important
buffer
system
within
red
blood
cells
and
tubules
of
the
kidney
is
the
diso-
dium/monosodium
phosphate
(NayHPO,)
buffer.
Excretion
of
H*
could
potentially
make
urine
so
acidic
that
excretion
would
be
physically
damaging
to
the
kidney.
Fortunately,
phosphate
Chapter
8
Acid-Base
Balance
161
Copyright
2020
Cengage
Leaming.
All
Rights
Reserved. May
not
be
copied,
scanned,
or
duplicated,
in
whole
or
in
part.
Due
to
electronic
rights,
some
third
party
content
may
be
suppressed
from
the
eBook
and/or
eChapter(s).
Editorial
review
has
deemed
that
any
suppressed
content
does
not
materially
affect
the
overall
leaming
experience.
Cengage
Learning
reserves
the
right
to
remove
additional
content
at
any
time
if
subsequent
rights
restrictions
require
i
Figure
8.2
Overall
Schema
for
Maintenance
of
Acid-Base
Balance
On
the
usual
mixed
diet,
pH
is
threatened
by
production
of
strong
acids
(e.g.,
sulfuric,
hydrochloric,
and
phosphoric),
which
result
mainly
from
protein
metabolism.
These
strong
acids
are
buffered
by
chemical
buffers
in
the
body.
Removal
of
extra
H*s
and
the
accompanying
anions
from
the
body
is
accomplished
by
renal
excretion.
When
the
kidneys
excrete
H*s,
they
add
new
bicarbonate
to
the
blood,
thereby
restoring
depleted
body
buffer
bases.
The
respiratory
system
eliminates
CO,
produced
by
metab-
olism.
CO,
is
not
a
threat
to
acid-base
balance,
provided
its
par-
tial
pressure
in
arterial
blood
is
kept
at a
normal
value.
©
}
Food
intake
¢
:
s/f
ee
Vv
Digestion,
absorption
v
Cell
metabolism
of
foodstuffs
»)
+
X
Sulfate,
chloride,
phosphate
anions
uf
co,
Ht
Depleted
HCO3~
replaced
CO,
blown
by
kidneys
off
by
lungs
Sulfate,
chloride,
phosphate
H*
soaked
up
excreted
by
chemical
by
kidneys
buffer
bases
(2.9,
HCOs)
H*
combined
with
urinary
buffers
excreted
by kidneys
Source:
Lauralee
Sherwood,
Human
Physiology:
From
Cells
to
Systems.
5th
ed.
copyright
©
2004,
p.
793.
helps
with
this
buffer
system
by
either
reabsorbing
HCO;
or
regenerating
additional
HCO;”
from
CO,
and
H,0.!?
Historically,
the
Henderson—Hasselbalch
equation
has
been
used
to
explain
the
interrelationships
between
HyCOs,
162
Part
3 Introduction to
Pathophysiology
Table
8.1
Chemical
Buffers
and
Their
Primary
Roles
Bicarbonate-carbonic
acid
buffer
Primary
ECF
buffer against
system
non-carbonic-acid
changes
Protein
buffer
system
Primary
ICF
buffer;
also
buffers
ECF
Primary
buffer against
carbonic
acid
changes
Hemoglobin
buffer
system
Phosphate
buffer
system
Important
urinary
buffer;
also
buffers
ICF
Note:
ECF,
extracellular
fluid;
ICF,
intracellular
fluid.
Source:
Reprinted
from
Sherwood
L.
Human
Physiology:
From
Cells
to
Systems.
9th
ed.
Boston
MA:
Cengage;
2016,
Table
15-6,
p.
552.
accepts
the
H*
and
a
weaker
acid
that
is
less
harmful
to
the
kidney
is
formed.
This
buffer
system
is
outlined
as follows:
NayHPO,+
H*
<
NaH,PO,+
Nat
Proteins
present
in
the
plasma
can
act
as buffers; their
contribution
is
most
important
intracellularly.
The
protein
buffer
system
acts in
the
same
fashion
as
the
bicarbonate—
carbonic
acid
buffer
system
in
that
protein accepts
the
H*.
Many
proteins
can
also
release
the
H7
if
alkalinity
increases.
The
proteins’
ability
to
act
in
both
situations
increases the
effectiveness
of
this
buffer
system.
Hemoglobin
within
the red
blood
cell
acts
as
the
most
important
buffer
in
blood.
Carbon
dioxide
diffuses
into
the
blood
asit
is
produced
throughout
the
body.
Most
of
the
CO)
will
combine
with
water,
forming
carbonic
acid. As
stated
earlier,
carbonic
acid
will
dissociate
to
bicarbonate
and
free
Ht.
Hemo-
globin
then
binds
the
H*.
The
reaction
is
reversed
as
blood
passes
through
the
lungs
and
becomes
oxygenated.
Oxygenated
hemoglobin
gives
up
the
H*
to
HCO3~
and
thus
carbonic
acid
(HCOs)
is
generated.
As
stated
earlier,
HCO,
dissolves
to
CO)
and
H,O.
CO,
is
then
expired
via
the
lungs
(see
Figure
8.3).
Respiratory
Regulatory
Control
The
next
line
of
defense
in
maintaining
acid—base
balance
is
respiratory
control.
The
lungs
have
the
ability
to
change
respi-
ratory
rate
and
depth
of
breathing
to
control
either
release
or
retention
of
CO)
and
hence
assist
in
management
of
acid—
base
balance.
This
control
system
is
very
sensitive
and
is
able
to
respond
spontaneously.
The
level
of
CO,
in
the
blood
controls
the
pH
of
the
cerebrospinal
fluid,
since
Ht
and
HCO;°
do
not
cross
the
blood-brain
barrier.
Changes
in
pH—specifically
the
level
of
CO,—are
detected
in
cerebrospinal
fluid
by
respiratory
cen-
ter
in
the
brain.
In
response,
respiratory
rate
changes
to
move
the
pH
toward
a
normal
range.
For
example,
when
acidosis
occurs
and
the
buffer
system
is
not
adequate
to
control
the
acidosis,
respiratory
rate
and
depth
will
increase
(hyperventilation).
This
allows
larger
amounts
of
CO,
to
be
expired.
In
a
situation
where
PaCO,
(see
chapter
endnote
1)
has
decreased
(alkalosis),
respirations
will
slow,
CO)
concentrations
will
increase,
and
pH
will
normalize.
Any
change
in
anatomy
or
physiology
of the
respiratory
system,
nervous
Copyright
2020
Cengage
Leaming.
All
Rights
Reserved.
May
not
be
copied,
scanned,
or
duplicated,
in
whole
or
in
part.
Due
to
electronic
rights,
some
third
party
content
may
be
suppressed
from
the
eBook
and/or
eChapter(s).
Editorial
review
has
deemed
that
any
suppressed
content
does
not
materially
affect
the
overall
leaming
experience.
Cengage
Learning
reserves
the
right
to
remove
additional
content
at
any
time
if
subsequent
rights
restrictions
require
it.
Figure
8.3
Transport
and
Exchange
of
Carbon
Dioxide
and
Oxygen
Carbon
dioxide
(CO2)
picked
up
at
the
tissue
level
is
transported
in
the
blood
in
three
ways:
(1)
physically dissolved,
(2)
bound
to
hemoglobin
(Hb),
and
(3)
as
bicarbonate
ion
(HCO3
).
Hemoglobin
is
present
only
in
the
red
blood
cells,
as
is
carbonic
anhydrase,
the
enzyme
that
catalyzes
the
production
of
HCO;.
The
H*
generated
during
the
production
of
HCO;
also
binds
to
Hb.
Bicarbonate
moves
by
facilitated
diffusion
down
its
concentration
gradient
out
of
the
red
blood
cell
into
the
plasma,
and
chloride
(CI)
moves
by
means
of
the
same
passive
carrier
into
the
red
blood
cell
down
the
electrical
gradient
created
by
the
outward
diffusion
of
HCO;
.
~
Alveoli
Tissue
cells
From
systemic
circulation
ca,
carbonic
anhydrase
Source:
L.
Sherwood,
Human
Physiology:
From
Cells
to
Systems.
9th
ed.
Figure
13-27,
p.
476.
system
control
of
respiration,
or
mus-
Figure
8.4
Control
of
the
Rate
of
Tubular
H*
Secretion
and
HCO3”
Reabsorption
cles
that
assist
in
breathing
will
affect
the
ability
of
the
respiratory
system
Alleviates
Buffers
to
respond
to
changes
in
pH.
The
next
line
of
defense
is
a
secondary
response
(often
referred
to as
com-
an
_,
pensation)
coordinated
by
the
kid-
neys,
described
in
the
next
section.
in
dealing
with
the
large
amount
of
nonvolatile
(fixed)
acids
since
these
cannot
be
expired
as
gases.
To
maintain
pH,
a
healthy,
nor-
and
H,0,
which
then
forms
HCO;
and
free
H*.
This
allows
Renal
Regulatory
Control
Control
of
Hydrogen
and
Bicarbonate
lons
The
kidney’s
role
in
controlling
both
H*
and
HCO;
is
a
critical
component
for
the
maintenance
of
pH
homeosta-
sis.
Respiratory
control
is
ineffectual
mally
functioning
kidney
will
reabsorb
the
majority
of
all
for
constant
regeneration
of
bicarbonate,
which
is
needed
to
HCO,"
that
is
needed
(see
Figure
8.4).
This
function
requires
buffer
the
fixed acids
being
continuously
released.
the
kidney
to
secrete
H*
(see
Figure
8.5),
which
combines
In the
situation
where
alkalosis
occurs,
the
kidney
will
with
HCO,
,
forming
H,CO3.
H,CO3
dissolves
to
form
CO,
respond
by
reducing
the
amount
of
HCO;
reabsorbed.
On
the
Chapter
8
Acid-Base
Balance
163
Copyright
2020
Cengage
Leaming.
All
Rights
Reserved.
May
not
be
copied,
scanned,
or
duplicated,
in
whole
or
in
part,
Due
to
electronic
rights,
some
third
party
content
may
be
suppressed
from
the
eBook
and/or
eChapter(s).
Editorial
review
has
deemed
that
any
suppressed
content
does
not
materially
affect
the
overall
learning
experience.
Cengage
Learning
reserves
the right
toremove
additional
content
at
any
time
if
subsequent
rights
restrictions
requize
it,
Figure
8.5
Hydrogen
lon
Secretion
Coupled
with
Bicarbonate
Reabsorption
in
a
Kidney
Tubular
Cell
Because
the
disappearance
of
a
filtered
HCO3°
from
the
tubular
fluid
is
coupled
with
the
appearance
of
another
HCO37
in
the
plasma,
HCO3
is
considered
to
have
been
“reabsorbed.”
Tubular
lumen
Peritubular
capillary
plasma
Type
intercalated
tubular
cell
KEY
=
Carbonic
anhydrase
=
=
Active
transport
¢
D
=
Secondary
active
transport
—
=
Passive
diffusion
———>
Chemical
reaction
a
=
Catalyzed
by
membrane-bound
ca
other
hand,
if
acidosis
occurs,
the
kidney
will
increase
secretion
of
H*
and
increase
the
amount
of
HCO"
reabsorbed.
Renal
reg-
ulatory
control
is
much
slower
than
respiratory
regulation
and
may
take
up
to
several
days
to
fully
respond
to
imbalances.*
Secretion
of
H*
isa
vital
component
of
the
renal
regulation
of
acid—base
balance.
The
minimum
pH
of
urine
in
humans
is
4.5.
If
pH
drops
below
4.5,
the
urine’s
acidity
becomes
harmful.
The
kidney
cannot
use
bicarbonate
as
a
buffer
since
it
cannot
be
excreted
at
the
same
time
as
the
hydrogen
ions.
Thus,
the
kidney
uses
two
other
buffers
(dibasic
phosphate
and
ammo-
nium)
to
prevent
damage
from
acidic urine,
as
described
in
the
next
section.
Other
Renal
Regulatory
Controls
The
base
NH;
(ammonia)
is
formed
in
renal
tubular
cells
from
the
amino
acid
glutamine.
Free
H*
combines
with
NH;
to
form
ammo-
nium
(NH,*).
Ammonium
cannot
cross
back
across
the
cell
membrane,
so
H™
is
trapped
and
is
thus
excreted
in
the
urine.
Table
8.2
Summary
of
Renal
Responses
to
Acidosis
and
Alkalosis
Alkalinization
toward
normal
Acidosis
SSE
Ga
Dibasic
phosphate
and
sulfur
both
function
to accept
H*
in
order
to
control
acid—base
balance.
In
a
situation
where
a
large
load
of
fixed
acids
is
produced,
the
kidney
will
respond
by
increasing
formation
of
acids
within
this
buffer
system.*°
This
may
occur,
for
example,
during
protein
catabolism.
Approximately
one-third
of
the
free
H*
is
excreted
as
phos-
phoric
acid
(HjPO,)
and
sulfuric
acid
(H)SO,).
Table
8.2
sum-
marizes
renal
responses
to
changes
in
acid—base
balance.
Effect
of
Acid
and
Base
Shifts
on
Electrolyte
Balance
Hydrogen
ions
and
bicarbonate
are
both
electrolytes.
Acid—base
changes
will
therefore
affect
concentrations
of
other
electrolytes
in
both
ECF
and
intracellular
fluid
(ICF).
For
example,
movement
of
HCO;
to
the
plasma
requires
the
exchange
of
another
negatively
charged
ion
so
that
electroneutrality
is
maintained.
Chloride
(CI)
is
the
ion
that
Normal
(zero;
all
Acidic
filtered
is
reabsorbed)
Source:
Reprinted
from
Sherwood
L.
Human
Physiology:
Fram
Cells
to
Systems.
9th
ed.
Boston
MA:
Cengage;
2016,
Table
15-8,
p.
557.
164
Part
3.
Introduction to
Pathophysiology
Copyright
2020
Cengage
Leaming.
All
Rights
Reserved.
May
not
be
copied,
scanned,
or
duplicated,
in
whole
or
in
part.
Due
to
electronic
rights,
some
third
party
content
may
be
suppressed
from
the
eBook
and/or
eChapter(s).
Editorial
review
has
deemed
that
any
suppressed
content
does
not
materially
affect
the
overall
learning
experience.
Cengage
Learning
reserves
the
right
toremove
additional
content
at
any
time
if
subsequent
rights
restrictions
requice
it,
moves
in
the
opposite
direction
of
HCO;
(as
shown
in
Figure
8.5).
Changes
in
potassium
(K*),
chloride
(CI-),
and
sodium
(Na*)
may
accompany
acid—base
disorders.”3*
Assessment
of
Acid-Base
Balance
It is
an
understatement
to
say
that
assessment
of
acid—base
disturbances
may
be
difficult.
This
difficulty
arises
because
of
the body’s
attempt
to
self-correct
changes
in
pH.
These
compensatory
or
secondary
responses
confuse
the
clinical
situation,
making
origin
of
the
disturbance
difficult
to
assess.
Assessment
of
acid—base
balance
requires
more
than
simply
examining
laboratory
values—it
needs
to
be
placed
into
the
context
of
the
patient's
current
medical
condition.
Examining
laboratory
values
elicits
only
the
current
state
of
blood
pH.
Furthermore,
because
the
body
can
actually
tolerate
changes
in
acid—base
balance
asymptomatically,
assessment
based
on
the
two-dimensional
model
that
is
generally
taught
is
not always
accurate.’
This,
of
course,
is
difficult
for
novice
clinicians,
but
with time
and
experience,
one
begins
to
be
able
to
piece
together the
puzzle
of
acid—base
disturbances.
Common
laboratory
measurements
of
arterial
blood
gases
(ABGs)
(see
Table
8.3)
and
serum
chemistries
will
provide
values
needed
to
initially
assess
acid—base
balance.®
These
include
arterial
measures
of
both
CO,
and
O,
(PaCO,
and
PaO,).
Additionally,
pH,
CO,
HCO;",
base
excess,
and
anion
gap
are
also
measured.
Even
though
both
base
excess
and
HCO;
are
measured,
they
directly
correlate,
so
it
is
Table
8.3
Normal
Arterial
Blood
Gas
(ABG)
Values
for
Assessment
of
Acid-Base
Balance
pH
7.35-7.45
pO2,
mmHg
280
pCO,
mmHg
35-45
HCO3,,
mEq/L
24-28
Base
excess,
mEq/L
>3
Anion
gap,
mmol/L
10-20
Anion
gap,
mEq/L 8-16
Q)
saturation,
%
295
not
necessary
to
evaluate
both
values.
See
Table
8.3
for
an
outline
of
normal
values of
ABG
parameters
and
analysis
of
ABGs.
When
evaluating
pH,
remember
that
in
humans
this
measures
the
ratio
of
acids
to
bases.
If
both
acid
and
base
increase
(or
decrease)
within
the
same
proportion,
pH
will
remain
steady.
It
is
only
when
one
changes
out
of
proportion
to
the
other
that
a
change
in
pH
will
be
measurable.
In
other
words,
just
because
pII
is
within
a
normal
range,
it
does
not
exclude
the
possibility
of
an
acid-base
disturbance.”
A
pH
<7.35
or
>7.45
indicates
acidosis
or
alkalosis,
respectively.
The
AG
represents
the
difference
between
unmeasured
anions
and
cations.
This
calculation
is
important
to
further
evaluate
situations
of
metabolic
acidosis.
AG
is
calculated
using
the
following equation:
Nat—(Cl-
+
HCO3;,).
The
reference
range
for
a
calculated
AG
is
8-16
mEq/L.””
Most
clinicians
do
not
use
K*
in
the
calculation
due
to
its
vari-
ability
in
acid—base
imbalances
but
this
assumption
is
con-
troversial.”*
When
assessing
acid—base
balance,
the
primary
response
is
determined
first
but
an
investigation
of the
sec-
ondary
response
or
compensation
as
well
allows
for a
com-
plete
assessment.
Application
of
these
values
is
discussed
throughout
the
following
sections.
Acid-Base
Disorders
There
are
four
major
types
of
simple
acid—base
disorders:
respiratory
acidosis,
respiratory
alkalosis,
metabolic
acido-
sis,
and
metabolic
alkalosis
(see
Table
8.4).
Combinations
of
each
of
these—indicating
a
mixed
disorder—can
and
often
do
occur.
The
only
combination
of
imbalances
that
is
not
a
pos-
sibility
is
simultaneous
respiratory
acidosis
and
respiratory
alkalosis,
since
obviously
hypoventilation
and
hyperventila-
tion
cannot
happen
together.
Respiratory
Acidosis
Respiratory
acidosis
occurs
when
there
is
an
excess
of
acid
in
relationship
to
base
caused
by
retention
of
carbon
dioxide.
This
generally
occurs
when
there
is
an
inability
of
the
lungs
to
expire
COQ).
As
the
level
of
CO)
rises,
hypercapnia
occurs,
more
carbonic
acid
(HyCO3)
is
formed,
and
pH
is
shifted
toward
acidosis.1”°
Table
8.4
Summary
of
CO,,
HCO;,,
and
pH
in
Uncompensated
and
Compensated
Acid-Base
Abnormalities
Normal Normal
Uncompensated
respiratory
acidosis
Decreased
Compensated
respiratory
acidosis
Normal
Uncompensated
respiratory
alkalosis
Increased
Compensated
respiratory
alkalosis
Normal
Uncompensated
metabolic
acidosis
Decreased
Compensated
metabolic
acidosis
Normal
Uncompensated
metabolic
alkalosis
Increased
Compensated
metabolic
alkalosis
Normal
Source:
Reprinted
from
Sherwood
L.
Human
Physiology:
From
Cells
to
Systems.
9th
ed.
Boston MA;
2016,
Table
15-9,
p.
562.
Normal Normal
20/1
Increased
Normal
20/2
(10/1)
Increased Increased
40/2
(20/1)
Decreased
Normal
20/0.5
(40/1)
Decreased
Decreased
10/0.5
(20/1)
Normal
Decreased
10/1
Decreased Decreased
15/0.75
(20/1)
Normal
Increased
40/1
Increased Increased
25/1.25
(20/1)
Chapter
8
Acid-Base
Balance
Copyright
2020
Cengage
Leaming.
All
Rights
Reserved.
May
not
be
copied,
scanned,
or
duplicated,
in
whole
or
in
part.
Due
to
electronic
rights,
some
third
party
content
may
be
suppressed
from
the
eBook
and/or
eChapter(s).
Editorial
review
has
deemed
that
any
suppressed
content
does
not
materially
affect
the
overall
leaming
experience.
Cengage
Learning
reserves
the
right
to
remove
additional
content
at
any
time
if
subsequent
rights
restrictions
requice
i
165

Etiology
Any
factor
that
inhibits
the
medullary
respiratory
center
can
affect
ventilation
and
thus
the
ability
to
release
CO.
Medications
such
as
opiates
or
sedatives
can
inhibit
respira-
tion.
Chronic
conditions
such
as
sleep
apnea
or
acute
events
such
as
cardiac
arrest
can
also
affect
normal
ventilation.
Diseases
that
affect
musculature
of
the
respiratory
system
and
chest
wall
can
result
in poor
ventilation.
These
may
include
neurological
conditions
such
as
myasthenia
gravis
or
extreme
obesity
such
as
seen
in
Pickwickian
syndrome.
Additionally,
any
injury
or trauma
to
the
chest
wall
can
potentially
result
in
an
inability
to
expire
adequate
amounts
of
carbon
dioxide.
Respiratory
diseases,
such
as
chronic
obstructive
pulmo-
nary
disease,
result
in
inability
to
maintain
adequate
oxygenation
or
release
of
carbon
dioxide.
Other
conditions
such
as
pneumo-
nia,
acute
pulmonary
edema,
or
pneumothorax
can
result
in
respiratory
acidosis.'”
Common
causes
are
outlined
in
Table
8.5.
Pathophysiology
In
respiratory
acidosis,
the
major
cellular
buffering
defense
available
is
expiration
of
CO,
by
the
lungs.
But
since
the
major
cause
of
respiratory
acidosis
is
respiratory
dysfunction,
this
buffering
system
is
typically
inefficient.
Body
stores
of
HCO;
are
released
in
order
to
maintain
the
appropri-
ate
ratio
of
CO)
to
HCO",
keeping
pH
within
a
normal
range.
During
acute
respiratory
acidosis,
the
kidney
regulatory
sys-
tems
do
not
have time
to
compensate,
since
these
only
begin
to
react
within
12
—
24
hours.
Chronic
respiratory
acidosis
is
less
critical
because
the
kidneys
have
more
time
to
provide
for
ongoing
compensation.
Renal
compensation,
which
works
over
a
longer
period,
includes
increased
excretion
of
H*
and
resorp-
tion of
HCO;
.
Other
renal
buffer
systems
such
as
the
use
of
ammonium
(NH,)
will
also
provide
a
secondary
response.
Clinical
Manifestations
Laboratory
values
in
acute
respiratory
failure
will
indicate
a
decreased
pH
and
an
ele-
vated
pCO.
Bicarbonate
levels
will
be
slightly
elevated
if
renal
compensation
has begun.
Compensatory
mechanisms
or
secondary
responses
allow
the
pH
to
remain
normal
but
serum
bicarbonate
and
arterial
pCO)
are
elevated.
Serum
Table
8.5
Common
Causes
of
Respiratory
Acidosis
¢
Hypoventilation
*
Chronic
obstructive
pulmonary
disease
Severe
pneumonia
or
asthma
¢
Acute
pulmonary
edema
*
Pneumothorax
*
Drugs:
opiate,
sedative,
anesthetic
overdose
(acute)
Excessive
oxygen
treating
chronic
hypercapnia
*
Sleep
apnea
¢
Neuromuscular
disease
such
as
amyotrophic
lateral
sclerosis
(ALS),
Guillain-Barré
syndrome,
spinal
cord
injury
©
Morbid
obesity,
Pickwickian
syndrome
Chest
wall
injury
or
skeletal
deformity
*
Aspiration
of
foreign
body
or
vomitus
¢
Laryngospasm,
laryngeal
edema,
severe
bronchospasm
Excessive
production
of
COz
*
Overfeeding,
especially
with
high-carbohydrate
components
of
nutrition
support
166
Part
3
Introduction
to
Pathophysiology
electrolytes
will
show
an
increase
in
serum
Ca*,
K*,
and
pos-
sibly
CI’
due
to
changes
in
renal
controls."*?
In
both
acute
and
chronic
respiratory
acidosis,
hypox-
emia
is
present.
This
reduced
level
of
oxygen
is
responsible
for
most
symptoms
associated
with
the
acidosis.
In
general,
a
more
acute
onset
will
result
in
increased
severity
of
symp-
toms.
Alterations
in
respiration
will
include
increased
respi-
ratory
rate
(hyperventilation)
and an
increase
in
depth
of
respirations,
Other
symptoms
are
result
of the
change
in
oxygenation
in
the
brain
and/or
a
decrease
in
neurotransmis-
sion.
These
include
restlessness,
apprehension,
lethargy,
mus-
cle
twitching,
tremors,
convulsions,
and
finally,
coma.2*
Treatment
Treatment
will
focus
on
correcting
the
under-
lying
condition causing
respiratory
changes.
Presence
of
hypoxemia
would
focus
treatment
on
increasing
oxygenation
through
administration
of
oxygen
or
provision
of
mechani-
cal
ventilation.
In
those
patients
with
chronic
hypoxemia,
it
is
crucial
to
realize
that
the
hypoxemia
may
be
providing
the
stimulus
for
ventilation.
If
oxygen
therapy reduces
hypox-
emia,
ventilation
may
acutely
decline
without
this
stimulus.
Respiratory
Alkalosis
Respiratory
alkalosis
(see
Table
8.6)
is
characterized
by
a
relative
excess
amount
of
base
(HCO;
)
as
a
result
of
a
reduc-
tion
of
CO).
This
acid—base
disturbance
is
generally
a result
of
conditions
causing
hyperventilation.
Rapid
breathing
results
in
a
decreased
PaCO).
Etiology
Hyperventilation
is
commonly
a
result
of
a
reduc-
tion
in
serum
oxygen
levels
(hypoxemia).
Hypoxemia
can
be
a result
of
respiratory
diseases
such
as
pneumonia,
asthma,
pulmonary
embolism,
or
pulmonary
edema,
or
of
exposure
to
high
altitudes.
Direct
stimulation
of
the
respiratory
center
in
the
brain
can
also
cause
hyperventilation
and
resulting
loss
of
CO).
For
exam-
ple,
disorders
of
the
CNS
such
as a
malignancy
or
stroke
can
affect
respiratory
centers
and
result
in
hyperventilation.
Hyper-
metabolic
states
such
as
in
fever
and
sepsis
can
directly
stimu-
late
hyperventilation.
Drugs—including
theophylline,
salicylates,
progesterone,
doxapram,
and
catecholamines—and
even
anxiety
or
other
types
of
emotional
distress
can
result
in
hyperventila-
tion.
Hyperventilation
can
also
occur
as
an
adaptive
response
to
high
oxygen
demands
during
strenuous
physical
activity.
Pathophysiology
The
acute
response
to
respiratory
alka-
losis
(within
the
first
24
hours)
is
a
shift
of
acid
from
the
ICF
to
the
ECF
with
an
accompanying
movement
of
bicarbonate
Table
8.6
Common
Causes
of
Respiratory
Alkalosis
Hyperventilation
*
Respiratory
infection;
pneumonia
¢
Asthma
©
Change
in
altitude
environment
(i.e.,
high
altitude)
©
Drugs
that
stimulate
respirations
(e.g.,
theophylline,
catecholamines)
°
Anxiety
©
Cerebrovascular
accident
°
Fever
and
sepsis
Copyright
2020
Cengage
Leaming.
All
Rights
Reserved.
May
not
be
copied,
scanned,
or
duplicated,
in
whole
or
in
part.
Due
to
electronic
rights,
some
third
party
content
may
be
suppressed
from
the
eBook
and/or
eChapter(s).
Editorial
review
has
deemed
that
any
suppressed
content
does
not
materially
affect
the
overall
leaming
experience.
Cengage
Learning
reserves
the
right
to
remove
additional
content
at
any
time
if
subsequent
rights
restrictions
requice
i
into
cells
in
exchange
for
chloride.
Additional
H*
is
syn-
thesized
by
an
increase
in
lactic
acid
derived
from
pyruvate
within
cells.
Shifts in
H*
are
generally
not
adequate
to
han-
dle
a
continued
decrease
in
PaCOy.
For
chronic
respiratory
alkalosis
(lasting
longer
than 24
hours),
a
secondary
renal
response
(compensation)
occurs.
The
kidneys
reduce
their
secretion
of
H*
(which
also
reduces
regeneration
of
HCO;
)
and
increase
their
excretion
of
bicarbonate
(HCO;
).
Clinical
Manifestations
In
acute
respiratory
alkalosis,
pH
is
>7.45
and
PaCOy
is
decreased. In
chronic
respiratory
alka-
losis,
pH
is
>7.45
and
plasma
HCO,
_
is
low.
In
both
situations,
alkalosis
may
be
accompanied
by
electrolyte
imbalances.
Labs
may
reveal
low
serum
levels
of
Kt
and
Ca*
as
well
as
high
levels
of
Cl.
Other
symptoms
of
respiratory
alkalosis
are
seen
in
the
cardiovascular,
central
nervous,
and
respiratory
systems.
Car-
diac
arrhythmias
may
be
noted.
Symptoms
of
the
respiratory
system
vary
but
may
include
frequent
yawning
and
deeper
breaths.
Symptoms
of
the
central
nervous
system
are
most
obvious
and
may
include
“lightheadedness,”
mental
confu-
sion,
anxiety,
and
seizures.
Patients
also
relate
paresthesias
with
cold
and
clammy
extremities.
Treatment
Correction
of the
underlying cause
of
respira-
tory
alkalosis
is
the
only
significant
treatment.
Correction
of
hypoxia
by
providing
oxygen
therapy
would
be
a
com-
mon
first
step.
If
the
cause
is
psychological
hyperventilation,
rebreathing
(see
chapter
endnote
2)
of
CO)
can
correct
the
symptoms.
Metabolic
Acidosis
Metabolic
acidosis
refers
to
all
types
of
acidosis
that
are
not
caused
by
excessive
CO).
It
can
result
from
either
excessive
loss
of
base
(HCO;
)
or
an
excessive
gain
of
fixed
(nonvolatile)
acids
(see
Table
8.7).
Metabolic
acidosis
can
develop
in
both
acute
and
chronic
conditions,
but
due
to
respiratory
compen-
sation,
it
is
most
often
a
chronic
condition
(see
Table
8.8).
Metabolic
acidosis
is
further
characterized
by
using
the
AG
calculation
to
determine
the
origin
of
the
disorder.*°°
Etiology
Conditions
that
result in
excessive
loss
of
bicarbon-
ate
from
the
gastrointestinal
system
or
from
renal
excretion
of
bicarbonate
can
result
in
metabolic
acidosis.
Diarrhea
is
the
most
common
cause.
Additionally,
HCO;
may
be
lost
from
an
ileostomy
or
from
pancreatic,
biliary,
or
intestinal
fistulas.”“
Table
8.7
Common
Causes
of
Metabolic
Acidosis
Kidney
loss
of
HCO3"
Chronic
kidney
disease
Systemic
loss
of
HCO3~
Diarrhea
Fistula
drainage
*
Excessive
production
of acid
Ketoacidosis
secondary
to
conditions
such
as diabetes
mellitus,
alcoholism,
or
starvation
Lactic
acidosis
secondary
to
conditions
such
as
diabetes
mellitus,
salicylate
overdose
Table
8.8
Respiratory
Adjustments
to
Acidosis
and
Alkalosis
Induced by
Nonrespiratory
Causes
Respiratory
rate
4
+
Tidal
volume*
i
+
Ventilation
t
+
Rate
of
CO,
removal
it Ay
Rate
of
carbonic
acid
+
t
formation
Rate
of
H*
generation
+
ity
from
CO
*Volume
of
oxygen
inhaled
and
exhaled
during
a
normal
breath.
Source:
Adapted
from
Sherwood
L.
Human
Physiology:
From
Cells
to
Sys-
tems.
9th
ed.
Boston
MA:
Cengage;
2016,
Table
15-7,
p.
5553.
Carbonic
anhydrase
inhibitors
such
as
the
drug
acet-
azolamide/Diamoz™
(used
as
an
antiseizure
medication
and
diuretic)
can
result in
excessive
loss
of
base
while
inhibiting
production
of
carbonic
acid
in
the
kidney.
In
the
condition
of
renal
tubular
acidosis,
ability
to
reabsorb
bicarbonate
is
decreased.
In
chronic
kidney
disease,
the
ability
to
restore
bicarbonate
may
fail
as
well.
Other
mechanisms
to
correct
acid—base
disturbances,
such
as
production
of
NH,*,
may
also
fail
as
renal
function
declines.
Metabolic
acidosis
may
also
result
from
situations
that
increase
the
amount
of
acid,
such
as
administration
of
ammo-
nium
chloride
(used
for
treatment
of
metabolic
alkalosis)
and
rapid
administration
of
IV
saline.
Accidental
poisoning
with
substances
such
as
salicylate
(aspirin),
ethylene
glycol
(anti-
freeze),
or
formaldehyde
can
result
in
metabolic
acidosis.
Lactic
acidosis
(see
Figure
8.6)
occurs
as a
result
of
increased
production
of
lactate
or
ketoacids.
High
levels
of
lactate
may
result
when
the
kidney
or
liver
fails
to
convert
lactate
to
pyruvate.
Diabetic
ketoacidosis,
one
of
the
most
common
causes,
results
in
metabolic
acidosis
due
to
both
increased
production
of
and
inability
to
metabolize
ketones
(see
Box
8.1).
In
both
starvation
and
chronic
alcoholism,
synthesis
of
ketoacids
is
increased.
Starvation,
with
its
reliance
on
fat
stores,
can
also
increase
synthesis
of
ketoacids
and
result
in
acidosis."
Figure
8.6
Lactic
Acid
Production
When
NAD
concentration
is
decreased
compared
to
NADH
+
H*,
the
scale
leans
in
the
direction
of
lactic
acid
production
and
not
pyruvic
acid
production.
Conditions
that
result
in
decreased
con-
centrations
of
NAD
include
decreased
oxygenation
of
the
tissues,
excessive
ketone
body
production
(as
in
diabetes),
and
metabo-
lism
of
ethanol.
NAD
Lactic
Acid
f
NADH
+
H*
Pyruvic
Acid
|
Chapter
8
Acid-Base
Balance
167
Copyright
2020
Cengage
Leaming.
All
Rights
Reserved.
May
not
be
copied,
scanned,
or
duplicated,
in
whole
or
in
part.
Due
to
electronic
rights,
some
third
party
content
may
be
suppressed
from
the
eBook
and/or
eChapter(s).
Editorial
review
has
deemed
that
any
suppressed
content
does
not
materially
affect
the
overall
leaming
experience.
Cengage
Learning
reserves
the
right
to
remove
additional
content
at
any
time
if
subsequent
rights
restrictions
requice
i

BOX
8
CLINICAL
APPLICATIONS
Diabetic
Ketoacidosis
One
out
of
every
four
emergency
room
visits
for
patients
with type
1
diabetes
mellitus
is
for
diabetic
ketoacidosis
(DKA).
It
has
been
estimated
that
over
$1
billion
is
spent
each
year
treating
this
condition
and
its
complications.
What
is
DKA,
and
how
is
this
condi-
tion related
to
the
acid-base
imbalances
you
have
learned
about
in
this
chapter?
Diabetes
mellitus
is
the
disease
caused
by
either
the
absence
or
inefficient
use
of
the
hormone
insulin
(see
Chapter
17).
Ketoacidosis
is
one
of
the
most
serious
acute
complications
of
type
1
diabetes
mel-
litus.
Diabetic
ketoacidosis
typically
develops
as a
result
of
infections
or
because
the
patient
does
not
take
adequate
amounts
of
insulin.
Without
adequate
insulin,
there
is
an
increased
dependence
on
lipids
as
the
primary
fuel
source.
The
increased
rate
of
lipolysis
results
in
the
production
of
ketones:
aceto-acetic
acid
and
hydroxybutyric
acid.
These
ketone
bodies
are
acids
that
lower
serum
pH.
The
kidney
reacts
by
excreting
the
ketone
bodies
in
the
urine
(ketonuria).
The
increased
levels
of
hydrogen
ions
are
buffered
by
plasma
bicarbonate.
This
combination
of
events
results
in
metabolic
acidosis.
High
levels
of
ketoacids
lead
to
an
increase
in
the
plasma
anion
gap.”
As
explained
in
this
chapter,
both
the
respiratory
and
renal
systems
serve
as
compensatory
or
secondary
mechanisms
in
acid-base
imbalance.
In
DKA,
as
pH
lowers,
respiratory
ventilation
changes
to
accommodate
the
need
to
reduce
pCO).
Respirations are
deep
and
labored—
referred
to
as
Kussmaul's
respirations.
Second,
the
renal
system
compensates
by
conserving
bicarbonate
(HCO;
>)
Furthermore,
urinary
excretion
of
positively
charged
cations
(Na*,
K*,
NH4*)
increases.
DKA
must
be
treated
quickly
and
accu-
rately
to
prevent
coma
and
death.
Providing
adequate
insulin,
fluids,
and
electrolytes
allows
the
correction of
the
metabolic
aci-
dosis
and
prevents
these
complications.
References
1.
Kitabchi
AE,
Umpierrez
GE,
Fisher
JN,
Murphy
MB,
Stentz
FB.
Thirty
years
of
personal
experience
in
hyperglycemic
crises:
diabetic
ketoacidosis
and
hyperglycemic
hyperosmolar
state.
J
Clin
Endocrinol
Metab.
2008;
93:
1541-52.
2.
Mendez
Y,
Surani
S,
Varon
J.
Diabetic
keto-
acidosis:
Treatment
in
the
intensive
care
unit
or
general
medical/surgical
ward?
World
J
Diabetes.
2017;
8:
40-4.
3.
De
Beer
K,
Michael
S,
Thacker
M,
et
al.
Diabetic
ketoacidosis
and
hyperglycemic
hyperosmolar
syndrome—clinical
guidelines.
Nurs
Crit
Care.
2008;
13:
5-11.
Pathophysiology
WhenH*
levels
increase,
the
bicarbonate—
carbonic
acid
buffer
system
is
stimulated.
This
shift
of
H*
into
ECF
reduces
serum
K*
at
the
same
time
in
order
to
maintain
equilibrium
between
the
ECF
and
ICE.
High
levels
of
H*
in
the
blood
stimulate
respiratory
cen-
ters
in
the
brain.
The
lungs
respond
by
increasing
rate
and
depth
of
breathing.
Finally,
the
kidneys
begin
their
com-
pensatory
response
by
increasing
their
excretion
of
H*
and
retention
of
HCO;~.
Renal
compensation
is
much
slower
than
respiratory,
and
if
kidney
disease
is
present,
effectiveness
of
the compensation
is
decreased.
Clinical
Manifestations
Symptoms
of
metabolic
acido-
sis
are
not
as
clear
as
those
of
other
acid—base
disturbances.
Changes
in
respiration
include
deep
labored
breaths
which
are
referred
to
as
Kussmaul
breathing.
The
cardiovascular
system
is
affected
by
decreased
contractility
and
response
to
catecholamines.
Vasodilation
may
cause
hypotension
and
dysrhythmias.
Neurologically,
lethargy
and
stupor
with
even-
tual
coma
are
observed
as
the
pH
falls
in
cerebrospinal
fluid.
In
chronic
renal
disease,
ongoing
metabolic
acidosis
relies
on
carbonate
from
bone
to
buffer
the
acid
load.
This
results
in
growth
failure
in
children
and
renal
osteodystrophy
in
adults.)
Treatment
Treatment
is
focused
on
the
underlying
cause
of
the
acidosis.
Correcting
pH
too quickly
can
cause
additional
complications.
The
goal
is
to
raise
systemic
pH
to
a
safe
level.
Metabolic
Alkalosis
Presence
of
an
excessive
amount
of
base
(HCO3,)
results
in
metabolic
alkalosis
(see
Table
8.9).
Generally,
this
acid—base
disturbance
is
caused
by
a loss
of
nonvolatile
acids
or
the
excessive
administration
of
bicarbonate
transfusion
within
whole
blood.
168
Part
3.
Introduction
to
Pathophysiology
Table
8.9
Common
Causes
of
Metabolic
Alkalosis
¢
Loss
of
acid
*
Vomiting
Nasogastric
suctioning
¢
Hypokalemia
Excessive
base
©
Intravenous
therapy
¢
Blood
transfusion
©
Excessive
or
chronic
use
of
antacids
Etiology
Clinical
situations
resulting
in
alkalosis
can
be
catego-
rized
as
either
those
conditions
involving
fluid
imbalance
(alka-
losis
with
volume
decrease)
or
those
without
fluid
imbalances
(alkalosis
without
volume
contraction).
Conditions
that
involve
fluid
imbalance
include
prolonged
vomiting,
nasogastric
(NG)
suction,
or
use
of
diuretics.
NG
suction
may
be
seen
in
post-
operative
patients
who
are
experiencing
ileus.
The
NG
suction
removes
gastric
secretions
in
prevention
of
vomiting
or
aspi-
ration.
Conditions
leading
to
alkalosis
that
do
not
involve
fluid
imbalance
would
include
hyperaldosteronism,
excessive
use
of
corticosteroids,
blood
transfusions,
chronic use
of
antacids,
and
excessive
administration
of
sodium
bicarbonate.“
Pathophysiology
Initiation
of
metabolic
alkalosis
begins
with
the
underlying
event
that
causes
either
an
excessive
loss
of
acid
or
accumulation
of
base.
This
could
be,
for
example,
prolonged
vomiting
that
results
in
decreased
concentration
of
HCI.
Normally,
the
kidney
will
compensate
for
the
decrease
in
nonvolatile
acid
by
generating
H*
and
decreasing
reab-
sorption
of
bicarbonate.
In
order
for
metabolic
alkalosis
to
progress,
other
events
need
to
occur
that
prevent
adequate
compensation
by
the
kidney.
Copyright
2020
Cengage
Leaming.
All
Rights
Reserved.
May
not
be
copied,
scanned,
or
duplicated,
in
whole
or
in
part.
Due
to
electronic
rights,
some
third
party
content
may
be
suppressed
from
the
eBook
and/or
eChapter(s).
Editorial
review
has
deemed
that
any
suppressed
content
does
not
materially
affect
the
overall
leaming
experience.
Cengage
Learning
reserves
the
right
to
remove
additional
content
at
any
time
if
subsequent
rights
restrictions
requice
i

In
situations
where
there
is
also
volume
depletion,
such
as
in
use
of
diuretics,
there
is
both
a
fluid
loss
and
a
subsequent
decrease
in
K*
levels.
To
maintain
serum
K*
levels
within
a
safe
range,
the
kidney
will
excrete
H*
in
exchange
for
K*.
Even
though
K*
may
increase,
the
loss
of
H*
results
in
generation
of
more
bicarbonate.
This
further
contributes
to
alkalosis.
Stored
blood
contains
citrate
as a
preservative.
If
an
individual
receives
a
large
amount
of
transfused
blood,
it
is
possible
the
body
will
convert
the
citrate
to
bicarbonate.
This
potentially
could
lead
to
metabolic
alkalosis.
Another
example
of
non-volume-related
alkalosis
is
in
the
condition
of
primary
or
secondary
hyperaldostero-
nism.
Increased
secretion
of
aldosterone
causes
the
kidney
to
increase
reabsorption
of
sodium.
This
is
accompanied
by
secretion
of
H*,
which
increases
regeneration
of
HCO;
.
Clinical
Manifestations
ABGs
in
metabolic
alkalosis
will
indicate
a
pH
of
>7.45
and
elevated
levels
of
HCO,
(>26
mEq/L).
Accompanying
electrolyte
imbalances
may
indicate
a
K*
<3.5
mEq/L
and
Cl"
<98
mEq/L.
If
compensation
by
the
respiratory
system
is
in
place
(see
Table
8.8),
PaCO,
will
remain
within
a
normal
range
or
be
slightly
elevated.
There
are
no
specific
signs
and
symptoms
for
metabolic
alkalosis.
Signs
and
symptoms
are
determined
by
accompanying
Table
8.10
Common
Mixed
Acid-Base
Disorders
Metabolic
acidosis
+
*
Cardiopulmonary
arrest
tespiratory
acidosis
*
Patient
with
COPD
goes
into
shock
*
PaCO,
too
high
*
Chronic
kidney
disease
with
fluid
HCO;
too
low
volume
excess
and pulmonary
edema
©
pH
very
low
*
Patient
with
DKA
receives
potent
opiate
or
barbiturate
Metabolic
alkalosis
+
respiratory
alkalosis
*
Patient
with
previously
compensated
respiratory
acidosis
caused
by
COPD
overventilated
on
mechanical
respirator
*
Hyperventilating
patient
with
CHF
or
hepatic
cirrhosis
who
is
vomiting
or
is
treated
with
potent
diuretics
or
nasogas-
tric
suction
*
PaCO;
too
low
*
HCO;
too
high
©
pH
very
high
*
Head
trauma
patient
with
hyperventila-
tion
treated
with
diuretics
Metabolic
acidosis
+
*
Lactic
acidosis
complicating
septic
shock
respiratory
alkalosis
*
Hepatorenal
syndrome
PaCO>
too
low
HCO3°
too
low
*
Salicylate
intoxication
pH
near
normal
*
Patient
with
COPD
who
is
vomiting
or
who
is
treated
with
NG
suction
or
potent
diuretics
* Adult
respiratory
distress
syndrome
Metabolic
alkalosis
+
respiratory
acidosis
*
PaCO;
too
high
*
HCO;
too
high
©
pH
near
normal
Note:
CHF,
congestive
heart
failure;
COPD,
chronic
obstructive
pulmonary
disease;
DKA,
diabetic
ketoacidosis;
NG,
nasogastric.
Source:
Reprinted
from
Price
SA,
Wilson
LM,
eds.
Pathophysiology:
Clinical
Concepts
of
Disease
Processes.
6th
ed.
St.
Louis,
MO:
Mosby;
2003,
Table
22-5,
p.
306.
Copyright
2003,
with
permission
from
Elsevier.
conditions
of
volume
deficit
or
electrolyte
abnormalities.
For
example,
in
the
situation
where
there
is
hypokalemia
and
a
decrease
in
ECF,
the
patient
may
experience
muscle
cramping,
weakness,
and
cardiac
arrhythmias.
Treatment
In
chloride-responsive
metabolic
alkalosis,
cor-
recting
volume
imbalance
with
isotonic
saline
with
added
KCL
will
correct
alkalosis.
Metabolic
alkalosis
that
does
not
involve
fluid
deficit
requires
treatment
of
underlying
causes
before
alkalosis
can
be
corrected.
In
severe
conditions,
use
of
a
carbonic
anhydrase
inhibitor
will
enhance
HCO,"
excretion.”
Mixed
Acid-Base
Disorders
Several
acid—base
disturbances
(see
Table
8.10)
can
coexist
in
complex
medical
problems.
For
instance,
this
may
occur
in a
patient
who
is
respiratory-compromised
and
is
unable
to
respond
to
a
situation
producing
a
metabolic
disorder.
This
could
also
occur
in
situations of
drug
overdose
where
different
medications
cause
both
respiratory
and
metabolic
responses.”
When
examining
ABGs,
a
mixed
disorder
should
be
suspected
when
PaCO,
and
HCO;
are
not
consistent
with
the
measured
pH.
A
mixed
disorder
may
also
be
present
when
the
compensatory/secondary
response
is
exaggerated.
For
example,
metabolic
alkalosis
and
respiratory
acidosis
may
occur
when
a
patient
with
chronic
obstructive
pulmonary
disease
receives
diuretics.
Assessment
of
Acid-Base
Disorders
To
place
all
of
this
into
perspective,
Table
8.4
summarizes
major
components
needed
to
assess
all
acid—base
disorders.
As
was
discussed
earlier
in
this
chapter,
ABG
measure-
ments
will
provide
data
needed
to
evaluate
acid—base
status
and
begin
steps
toward
intervention.
8.4
CONCLUSION
Remembering
basic
concepts
related
to
acid—base
balance
will
keep
you
on
track
in
evaluating
these
complex
clinical
situations.
¢
The
scale
for
measuring
acidity
or
alkalinity
of
a
fluid
is
the
measurement
of
pH.
Simply
stated,
pH
is
the
ratio
of
bases
to
acids.
Normal
pH
in
humans
is
7.35—7.45.
The
pH
is
maintained
in
ratio
of
20:1
base
to
acid
within
body
fluids.
There
will
be
no
change
in
pH
if
the
ratio
remains
stable,
but
changes
in
either
portion
of
the
ratio
will
result
in
changes
in
pH.
+
The
largest
source
of acid
within
the
body
is
carbonic
acid.
‘We
measure
concentration
of
CO)
as
an
indirect
measure
of
acidity,
Concentration
of
CO)
is
expressed
as
PaCO).
+
The
lungs
are
the
primary
regulators of
CO)
levels.
+
The
largest
source
of
base
is
HCO;
,
which
is
regulated
primarily
by
the
kidneys.
+
Respiratory
acidosis
is
a
result
of
retention
of
CO»,
whereas
respiratory
alkalosis
is
a
result
of
hyperventila-
tion
and
a
subsequent
decrease
in
CO)
levels.
+
Metabolic
acidosis
occurs
when
there
is
retention
of
fixed
acids
or
excessive
loss
of
bases.
Metabolic
alkalosis
is
a
result
of
excessive
loss
of
fixed acids
or
retention
of
bases.
Chapter
8
Acid-Base
Balance
169
Copyright
2020
Cengage
Leaming.
All
Rights
Reserved.
May
not
be
copied,
scanned,
or
duplicated,
in
whole
or
in
part.
Due
to
electronic
rights,
some
third
party
content
may
be
suppressed
from
the
eBook
and/or
eChapter(s).
Editorial
review
has
deemed
that
any
suppressed
content
does
not
materially
affect
the
overall
leaming
experience.
Cengage
Learning
reserves
the
right
to
remove
additional
content
at
any
time
if
subsequent
rights
restrictions
requice
i

APPLICATION
OF
THE
NUTRITION
CARE
PROCES
ACI
BASE
IMBALANCE
INTRODUCTION
Mr.
N
visits
his
physician
with
complaints
of
the
following:
pain,
dizziness,
and
difficulty
breathing.
Mr.
N's
daughter
also
indi-
cates
he
has
become
more
and
more
confused
over
the
previous
24
hours.
As
the
physician
proceeds
to
his
physical
exam,
he
notes
that
blood
pressure
is
out
of
the
normal
range
and
respi-
ratory
rate
and
heart
rate
are
high.
Further
tests
indicate Mr.
N’s
hemoglobin
is
low
while
his
white
blood
cell
count
is
elevated.
chronic
obstructive
pulmonary
disease,
and
a history
of
coronary
heart
disease.
Which
of
these
might
interfere
with
his
ability
to
maintain
a
normal
acid-base
balance?
NUTRITION
ASSESSMENT:
BIOCHEMICAL
DATA
3.
The
physician
has
ordered
arterial
blood
gases.
Values
you
note
as
abnormal
are
as
follows:
pH
7.47;
pCO
46
mmHg;
pO,
83
mmHg;
HCO;
32
mEd/L.
a.
Classify
the
pH.
1.
Outline
items
from
Mr.
N's
case
that
fall
into
each
of
the
b.
Assess
pCO>.
following
categories:
c.
Assess
HCO;.
a.
Signs
d.
Do
you
see
any
indication
of
compensation?
Why
or
b.
Symptoms
why
not?
c.
Laboratory
abnormalities
2.
Upon
examination
of
his
medical
record,
you
find
that
Mr.
N
has
the
following
diagnoses:
renal
insufficiency,
©
Identify
the
primary
acid-base
disorder.
f.
How
do
his
medical
diagnoses
relate
to
this
acid-base
imbalance?
CHAPTER
REVIEW
QUESTIONS
1.
Define
the following
terms:
pH,
volatile
acid,
nonvolatile
(fixed)
acid,
and
buffer.
2.
What
organ
controls
the
level
of
pCO,
in
the
blood?
What
organ
controls
HCO;
in
the
blood?
3.
What
is
the
essential
problem
in
respi-
ratory
acidosis?
Respiratory
alkalosis?
4.
What
is
the
most
important
differ-
ence
between
metabolic
acid—base
disorders
and
those
of
a
respiratory
origin?
5.
Name
some
conditions
that
might
result
in
respiratory
acidosis.
6.
Name
some
conditions
that
might
result
in
metabolic
acidosis.
7.
What
is
an
anion
gap?
.
How
can
respiratory
mechanisms
compensate
for
metabolic
alkalosis?
Are
there
any
major
limitations
to
this
compensation?
ENDNOTES
1.
Reported
blood
gas
abbreviations.
The
letter
“P”
before
CO,
or
O,
is
the
partial
pressure
of
the
gas,
but
it
could
be
of
arterial,
venous,
or
mixed
blood.
When
the
letters
“Pa”
are
in
front
of
the
gas,
it
is
the
partial
pressure
of
the
gas
in
the
arterial
blood.
2.
Rebreathing
into
a
paper
bag:
Have
you
heard
of
doing
this
for
someone
when
he
or
she
is
nervous
and
breathing
too
fast
(e.g,,
for
hyperventilation)?
The
rationale
is
that
rebreathing
into a
paper
bag
will
allow
the
person
to
replace
the
carbon
dioxide
“blown
off”
while
hyperventilating.
REFERENCES
1.
Sherwood
L.
Fluid and
acid-base
balance.
In:
Human
Physiology:
From
Cells
to
Systems.
9"
ed.
Boston
MA:
Cengage;
2016:
535-64.
2.
DuBose
TD,
Jr.
Acidosis
and
alkalosis.
In:
Kasper
D,
Fauci
A,
Hauser
S,
Longo
D,
Jameson
J,
Loscalzo
J,
eds.
Harrison's
Principles
of
Internal
Medicine.
19"
ed.
New
York,
NY:
McGraw-Hill;
2014.
http://accessmedicine.mhmedical.com/con-
tent.aspx?bookid=1130&
sectionid=79726883,
accessed
August
9,
2018.
3.
Berend
K.
Acid-base
pathophysiology
after
130
years:
confusing,
irrational
and
controversial.
J
Nephrol.
2013;
26:
254-65.
4,
American
Society
for
Parenteral
and
Enteral
Nutrition
(A.S.PE.N).
Fluids,
Electrolytes
and
Acid-Base
Disorders
Handbook.
Canada
T,
170
Part
3
Introduction to
Pathophysiology
Tajchman
SK,
Tucker
AM,
Ybarra
JV,
eds.
Silver
Spring
MD:
ASPEN;
2015.
5.
Morris
CG,
Low
J.
Metabolic
acidosis
in
the
critically
ill:
part
1.
Classification
and
pathophysi-
ology.
Anaesthesia.
2008;
63:
294-301.
6.
Morris
CG,
Low
J.
Metabolic
acidosis
in
the
critically
ill: part
2.
Causes
and
treatment.
Anaes-
thesia.
2008;
63:
396-411.
7.
Kraut
JA,
Nagami
GT.
The
serum
anion
gap
in
the
evaluation
of acid-base
disorders:
what
are
its
limitations
and
can
its
effectiveness
be
improved?
Clin
J
Am
Soc
Nephrol.
2013;
8:
2018-24.
8.
Ayers
P,
Dixon
C.
Simple
acid-base
tutorial.
J
Parenter
Enteral
Nutr.
2012;
36:
18-23.
9,
Hamm
LL,
Hering-Smith
KS,
Nakhoul
NL.
Acid—base
and
potassium
homeostasis.
Semin
Nephrol.
2013;
33:
257-64.
10.
Martinu
T,
Menzies
D,
Dial
S.
Re-evaluation
of
acid—base
prediction
rules
in
patients
with
chronic
respiratory
acidosis.
Can
Respir
J.
2003;
10:
311-15.
11.
Reddy
ST,
Wang
CY,
Sakhaee
K,
Brinkley
L,
Pak
CY.
Effect
of
low-carbohydrate
high-protein
diets
on
acid—base
balance,
stone-forming
pro-
pensity,
and
calcium
metabolism.
Am
J
Kidney
Dis.
2002;
40:
265-74.
Copyright
2020
Cengage
Leaming.
All
Rights
Reserved.
May
not
be
copied,
scanned,
or
duplicated,
in
whole
or
in
part.
Due
to
electronic
rights,
some
third
party
content
may
be
suppressed
from
the
eBook
and/or
eChapter(s).
Editorial
review
has
deemed
that
any
suppressed
content
does
not
materially
affect
the
overall
leaming
experience.
Cengage
Learning
reserves
the
right
toremove
additional
content
at
any
time
if
subsequent
rights
restrictions
requice
it,

1
Response
Student’s Name
Institutional Affiliations
Course
Date

2
Response
As you argue, I agree with you that science and God collide. In my understanding, I think
that nutrition genomics is an unethical practice because it contradicts God's work. As a Christian,
I believe that it is inhumane to use humans as research subjects and use their genes to perform
experiments. God created humans with perfection, and no science should be used to modify
human health. On the other hand, nutrition genomics has improved the general well-being of
individuals, even if I don't support it for moral reasons.1 The science behind nutrition genomics
has significantly helped create medicines that treat complications such as cardiovascular disease,
diabetes, cancers, and hypertension.1 As you argue, I agree that nutrition professionals aim to
advise individuals on specific nutrition to optimize their health. On top of this, I would like to
support your assertion by stating that nutrition genomics knowledge guides nutrition
professionals in knowing the best diets for specific individuals. Concerning gene-environment
interaction, analyzing the relationship between environmental and genetic factors helps scientists
develop solutions to various diseases, like nutrition and physical and social surrounding.2 For
example, nutrition professionals advise individuals on specific foods that they should take to
prevent the development of specific diseases. This applies when scientists establish that an
individual's genes are susceptible to a specific disease. The dietary prescription that reacts well
with the gene may help delay or prevent the development of a disease the person is at high risk
of getting.

3
References
1. Introduction to pathophysiology, (n.d).Introduction: Introduction to pathophysiology.
2. Public health nutrition, (n.d). Gene-environment interactions and public health nutrition.

