


At least 6 reliable articles- An article can address one or all of the
elements below.
You also have to identify a source to gather epidemiological
data

ADOLESCENT IMMUNIZATION PROPOSAL 1
Adolescent Immunization Proposal
Immunization for Young Adult
Towson University
Adolescent Immunization Proposal

ADOLESCENT IMMUNIZATION PROPOSAL 2
To achieve optimal health and wellness, taking heed to the utmost significance of
immunizations is critical. In the development of our program, we decided to focus on the
adolescents and their parents as our target population. Our program proposal demonstrates the
condition, intervention, and issue of adolescent immunizations. The American Academy of
Pediatrics reviewed the 2016 National Immunization Survey-Teen (NIS-Teen) by the Centers for
Disease Control (CDC) data on the human papillomavirus (HPV) vaccine (Hasten & Pickering,
2017). The review stated that the HPV vaccine can prevent 90% of cancer attributed to HPV
(Hasten & Pickering, 2017). The Healthy People 2020 overarching goal for adolescents is to
increase routine vaccination for adolescents (HHS, 2018). One of the Healthy People 2020
specific goal objectives (increased adolescent vaccinations) that the two-year intervention will
focus on is to increase the percentage of female adolescents aged 13 through 15 years who
receive 2-3 doses of the recommended HPV vaccine (HHS, 2018). Healthy People 2020 details
that in 2008, the HPV vaccine completion was 16.6%, this went up to 28.1% in 2012. In 2016,
45.1% of female adolescents aged 13-15 years old received appropriate dose completion of HPV
vaccine (HHS, 2018). Healthy People 2020 targets an 80% HPV vaccine completion rate by
2020 (HHS, 2018). The objectives of this two-year intervention are to increase HPV vaccine
completion of female adolescents 13-15 years old by 10% as well as increased vaccine coverage
for Tdap and Meningococcal Conjugate.
In addition, one of the three recommended vaccines for adolescents is tetanus-diphtheria-
acellular pertussis (Tdap) (Hasten & Pickering, 2017). One of the Healthy People 2020
objectives is to increase the vaccination coverage level of 1 dose of Tdap booster vaccine for
adolescents aged 13 through 15 years (HHS, 2018). Tdap has the highest vaccine coverage for
adolescents. 86% of adolescents were covered in 2015, this increased to 88% in 2016 (Hasten &

ADOLESCENT IMMUNIZATION PROPOSAL 3
Pickering, 2017). The two-year intervention will increase vaccination coverage level of 1 dose of
Tdap booster by 4% in addition to coverage for Tdap and Meningococcal Conjugate vaccines.
MenACWY, the meningococcal conjugate vaccine series contains two doses (Hasten &
Pickering, 2017). The first dose is given by age 11, and the second dose by age 16 (Hasten &
Pickering, 2017). The Healthy People 2020 objective is to also increase the vaccination coverage
of 1 dose meningococcal conjugate for adolescents ages 13 through 15 (HHS, 2018). In 2016,
only 39% of adolescents received at least both doses of the MenACWY (Hasten & Pickering,
2017). 82% of adolescents received at least one dose (Hasten & Pickering, 2017). This infers that
adolescents do not return by age 16 for the second MenACWY dose (Hasten & Pickering, 2017).
There was a 6% increase of adolescents who received at least two doses of the meningococcal
conjugate vaccine series from 2015-2016 (Hasten & Pickering, 2017). The two-year intervention
aims to increase adolescents who are vaccinated with at least 2 doses of meningococcal
conjugate vaccine series by 12%.
The sources that we utilized to acquire epidemiological data for our adolescent
immunization program proposal are secondary data. These include the Centers of Disease
Control, Department of Health and Human Services (HHS), and other peer-reviewed articles and
websites from various academic/health journals, as well as through Healthy People 2020.
ARTICLES
Burns, J.L., Walsh, L.J., & Popovich, J.M. (2010). Continuing Education: Practical Pediatric and
Adolescent Immunization Update. The Journal for Nurse Practitioners, Volume 6, Issue
4.
Burns, Walsh, & Popovich (2010), discussed the roles of Nurse Practitioners (NPs) in
vaccinating children. The authors’ gave updates to the current immunization trend and its

ADOLESCENT IMMUNIZATION PROPOSAL 4
relation to Healthy People 2010. The authors noted the success of vaccines in eradicating
smallpox in 1977 and poliomyelitis from the Americas in 1991. The authors also discussed
barriers to immunization such as predisposing factors of parental immunization concerns in the
immunization schedules. In addition, barriers to immunization also include health disparities
where African American low-income children are less immunized than their Caucasian
counterpart. Adolescents 13-17 years of age immunization data shows African-Americans had
only 36% immunization against varicella and 41.7% against Tdap. Burns, Walsh, & Popovich
(2010), detailed issues with adolescent immunization and noted that there are no mandatory
preventative healthcare visits for teens. In the article, they noted that there were disparities in
HPV vaccines between African-Americans and Caucasians, as Caucasians were more informed
about HPV. African-Americans were less likely to see cervical cancer as an issue. However,
there were high vaccination rates in Latina women and their daughters. The primary reason for
the vaccination is concern about cancer.
This source provides support for the need of immunization intervention for adolescents.
Only one-third of adolescents reached the 90% immunization in the Healthy People 2010 goal.
Adolescents often face enabling factors such as un-insurance or underinsurance in accessing
healthcare. Enabling factors that contribute to adolescents not receiving vaccines also include an
absence of a nationwide immunization tracking system, which makes it difficult for parents to
receive federally mandated vaccine information statements (VIS) on immunizations their
children receive. These enabling factors can be reinforced by adolescents lacking the support
they need and having to make their own healthcare decisions. Predisposing and reinforcing
factors can also include parents and families lack of knowledge which can result in missed
vaccine opportunities, because of a lack of understanding in vaccine consent laws. A solution to

ADOLESCENT IMMUNIZATION PROPOSAL 5
these factors is school-based health care centers (SBHCs), which can provide immunizations in
places teens are already attending.
Federico, S.G., Abrams, L., Everhart, R.M., Melinkovich, P., & Hambidge, S.J. (2010).
Addressing Adolescent Immunization Disparities: A Retrospective Analysis of School-
Based Health Center Immunization Delivery. American Journal of Public Health, Vol
100, No. 9.
The authors conducted a retrospective analysis on the immunization delivery of school-
based health center (SBHC) vs. community health centers (CHCs). The two immunization
delivery centers are part of the Denver Health multilevel health system which has 8 CHCs and 12
SBHCs. The clinics analyzed were in urban centers serving a large non-English speaking Latino
population group who were either covered through Medicaid, SCHIP or were uninsured. A
retrospective analysis cohort was conducted on 17,349 children and adolescents ages 12-18,
receiving care in the Denver Health system over the course of two years. 47% received
immunization through CHCs, 38 % through SBHCs and 15% received care through both.
Eventually, individuals who used both were classified as either CHC or SBHC depending on
which center they most utilized.
CHC patients were majorly female, SBHC patients were more likely to be Hispanics,
uninsured and have multiple visits. Children and adolescents who had access through SBHCs
were more up to date for hepatitis B: 84%. Tdap at SBHCs were 71% compared to 62% at
CHCs. Varicella was 20%, at CHCs 13%; measles, mumps and rubella (MMR) 89% at SBHCs,
83% at CHCs. HPV for adolescents age 16-18 were 18% at SBHCs and 12% at CHCs;
HPV/Tdap/MCV4 immunization series for female adolescents age 16-18 were 17% SBHCs and

ADOLESCENT IMMUNIZATION PROPOSAL 6
11% CHCs. Hepatitis B, Tdap, varicella and HPV for 16-18 year olds were more likely to be
completed in SBHCs while tetanus/diphtheria were more up to date in CHCs. SBHCs and CHCs
had no significant impact on hepatitis A or MCV4 vaccinations. The retrospective study focused
on children and adolescents in a high-risk population, also adolescents are a group at risk for
under immunization. SBHC patients had Tdap and MCV4 rates far superior compared to the
national average and HPV completion were equal to the national average.
The source provides detailed success of various vaccinations for youth and adolescents.
Adolescents can face enabling factors such as un-insurance and underinsurance when trying to
access healthcare. SBHCs are successful in reaching adolescents in an urban integrated health
system. SBHC can enable adolescents to receive vaccinations. Children and adolescent’s patients
in SBHCs were more likely to complete a vaccine series and were more likely to receive single-
dosed vaccines. While 43% SBHC users were uninsured, SBHCs were able to overcome
utilization barriers. SBHCs are positive enabling factors able to capitalize on students’
attendance at school. They are also great to use to developed immunization registries which is
very useful to capture data on populations who receive care at multiple sites. SBHCs have the
resources and primary care physicians, and are able to see patients for multiple visits. They can
also use reminder calls and are able to see patients regardless of ability to pay. Parents also do
not have to miss work, worry about transportation, patients also do not have to miss class to
receive their immunization. However, federal dollars are not used for operational costs for
SBHCs. Private and public payers do not reimburse for services received at SBHCs. Policies to
support SBHCs could help deliver increased immunizations to children, adolescents and adults in
underserved populations.

ADOLESCENT IMMUNIZATION PROPOSAL 7
Salmon, D.A., Dudley, M.Z., Glanz, J.M., & Omer, S.B. (2015). Vaccine Hesitancy Causes,
Consequences, and a Call to Action. American Journal of Preventive Medicine and
Elsevier Ltd, 49(6S4): S391–S398.
Vaccine hesitancy reflects the concern of perceived risks and benefits of vaccination.
Vaccine hesitancy is described as the delay or refusal to accept vaccines and the concerns of
even those who do vaccinate fully and regularly. Attitudes and beliefs help measure vaccine
acceptance, delay and refusal. Parents who are hesitant, despite vaccinating on time are
vulnerable to misinformation. The authors noted that fear of vaccines include a coincidental
relationship between vaccines when they’re given an adverse health outcome. Furthermore, the
increase of vaccines has gone from 15 to 24 doses from 1995 to 2015, making vaccines appear as
the cause for childhood diseases. Distrust in the pharmaceutical industry and the change in the
medical model from parents trusting pediatricians to tell them what to do for the best interest of
their child to parents wanting to be part of the decision making.
The National Immunization Survey (NIS) did a random digital survey of households with
children 19-35 months, along with a mailed provider survey to determine immunization histories
combined with parental attitudes, beliefs and decision making along with Parental knowledge
and experiences over the course of two years (2000-2002). Non-Hispanic white married English-
speaking mothers with high maternal age, education and incomes were surveyed. The 2003
compiled data found that 31.8% of parents delayed vaccines for their children, 44.8% reported
concerns about vaccine safety, 36.1% worried about their child falling ill. 7.7% of parents missed
vaccine appointments, 5.6% worried about vaccine cost and 8.5% had other concerns.
NIS data from 2009 showed an increase of parental vaccine delay from 21.8% from 2003
to 39.8% in 2009. 95% of the population must be vaccinated for herd immunity to be beneficial

ADOLESCENT IMMUNIZATION PROPOSAL 8
to the community. But, vaccine hesitancy and refusal have resulted in outbreaks of measles,
varicella, and pertussis. The authors noted that first-time pregnant mothers may be the target of
vaccine education because they’re attitudes on childhood vaccines are not yet set. The authors
also noted that in a systematic review of vaccine interventions there were no evidence of
effective interventions. Also, the authors warn that pro-vaccine messages are ineffective and
messages to correct people on vaccine misinformation, backfired. The authors suggest making
vaccines a part of a routine care may be more effective.
The source is useful in understanding data on vaccine hesitancy and parental attitudes and
beliefs along with knowledge and experiences. The article noted enabling factors of vaccine
hesitancy such as lack of legislation to address public confidence in vaccines. The vaccine safety
budget as reported by the CDC in 2011 was $20 million out of $4 billion overall vaccine budget.
This has remained the same since 2011. Other predisposing factors to vaccine hesitancy include
fear of coincidental adverse health such as a child developing autism around the same age that
vaccines are given. An intervention in which concerns about vaccines are laid to rest without
falling into the trap of ineffective pro-vaccine messages can improve acceptance of
immunization by parents for the benefit of their child.
Greenfield, L. S., Page, L. C., Kay, M., Li-Vollmer, M., Breuner, C.C., & Duchin, J.S. (2015).
Original article: Strategies for Increasing Adolescent Immunizations in Diverse Ethnic
Communities. Journal of Adolescent Health, 56, S547-S53.
https://doi.org/10.1016/j.jadohealth.2014.10.274
Health education and health promotion include outreach to communities with a goal to
increase awareness on disease prevention and treatment. Greenfield, Page, Kay, Li-Vollmer,

ADOLESCENT IMMUNIZATION PROPOSAL 9
Breuner & Duchin (2015) conducted a research study on three communities (i.e., Hispanic,
Somali, and Ethiopian) located in King County in the State of Washington, and tackled the issue
of adolescent vaccinations. In their study, the authors found that there are several barriers that
hinder adolescents in these three communities on participating in acquiring vaccinations,
specifically for Tdap, MCV4, and HPV. The authors addressed the issue of lack of vaccinations
by collaborating with a state governmental department as well as a nonprofit organization both
located in Washington. These entities worked together with the authors for adolescents to gain
increased access to vaccinations by overcoming barriers- they conducted a thorough study of the
factors that are involved in the issue of lack of vaccinations. They used several methods in their
study such as in-person surveys administered to adolescent participants including their parents
and focus groups where mothers with adolescent children were recruited.
Through the in-person surveys and focus groups, the authors found that the key promoter
of health education (in this case concerning the awareness and importance of vaccinations) is
through the health care providers, specifically with physician’s recommendation. The authors
covered in the discussion section of the article that the insufficiency of knowledge and awareness
concerning vaccinations amongst the participants in the study is one of the main reasons of the
lack of participation in acquiring vaccinations. “Beliefs and misperceptions” (S51) concerning
diseases as well as limited language translation about vaccinations, affect participants’
engagement in obtaining recommended vaccinations, as stated in the article. In conclusion, the
need for active outreach in health education and health promotion conducted by health care
providers is crucial for these three communities to thrive in their overall health and wellness.

ADOLESCENT IMMUNIZATION PROPOSAL 10
Salazar, K., Seib, K., Underwood, N., Gargano, L., Sales, J., Diclemente, R., Murray, D.,
Morfaw, C., & Hughes, J. (2016, July). Recommendations for Structure and Content
for a School-Based Adolescent Immunization Curriculum. Health Promotion
Practice, 17(4), 512-520. htttps://doi.org/10.1177/1524839915627458
The school communities play a vital role in educating the youth, specifically in
health- related issues as well as in taking part in preventative measures. In the article by Salazar,
Seib, Underwood, Gargano, Sales, Diclemente, Murray, Morfaw, & Hughes (2016), they noted
that the impartation of knowledge and awareness on adolescent immunizations within the school
system is necessary, for the community to participate in receiving immunizations, thus to be
protected from the spread and outbreak of diseases. The authors made a distinction on how
childhood immunizations are more utilized than adolescent immunizations; hence, they created a
plan of intervention to be carried in schools through incorporating adolescent immunizations in
the school curriculum, with teachers as part of the study population.
The authors emphasized on the article that students spend a significant amount of their
time within the school environment; making the school a “promising location for immunization
interventions.” (p. 513). The authors utilized the Health Belief Model (HBM) and The Theory of
Reasoned Action in their study design. As for the methods used for the intervention, the authors
applied focus groups with the participation of two researchers who facilitate the discussion
within the groups. Essentially, the intervention on the increased education on adolescent
immunization took place in the school setting- by having it incorporated in the academic
curriculum. Through the focus group discussions, the teachers (population) were able to provide
feedback as well as voice out their opinions and observances concerning adolescent
immunizations as part of the academic curriculum of students.

ADOLESCENT IMMUNIZATION PROPOSAL 11
In the results section of the article, the authors found that the recommendations the
teachers provided in the focus group discussions can help enhance student awareness and
knowledge on the topic of adolescent immunizations. The authors noted that there are various
ways to improve the school-based curriculum by including “audiovisual supplementation” as
well as “vaccine games and activities” (p. 515) with a goal of increasing adolescent participation
on receiving immunizations. In addition, the authors identified that incorporating the subject of
adolescent immunizations in the academic curriculum is feasible and that it will benefit the
community as a whole, as school administrators and educators are also in support of the
intervention. Through conducting a thorough study and review of the immunization intervention
in school, the authors stated the need to have additional information available
online/electronically for a more convenient way for students to access health and immunization
information. Although there are strengths in the study such as the positive influence in attitudes
and behaviors of students through the intervention, there are also limitations that were present
such as the absence of parents’ participation, which the authors noted might have helped in the
overall outcome of the curriculum intervention.
Bar-Shain, D., Stager, M., Leon, J., Kaelber, D., & Runkle, A. (2015). Direct messaging to
parents/guardians to improve adolescent immunizations. Journal of Adolescent Health,
56(5), S21-S26. https://doi.org/10.1016/j.jadohealth.2014.11.023
The rate of adolescent immunization in the United States is falling behind; particularly
for immunizations for tetanus, diphtheria, and Tdap. According to Bar-Shain, Stager, Leon,
Kaelber, & Runkle (2015), there are several factors that affect this low rate of adolescent
immunizations. These factors include racial and ethnic background as well as one’s

ADOLESCENT IMMUNIZATION PROPOSAL 12
socioeconomic status. The subjects of the research study are adolescents 11-18 years of age, who
had “at least one ambulatory primary care encounter” (S22), and who have not completed the
required immunizations for tetanus, diphtheria, and Tdap, lacking “at least one” of these
immunizations (S22).
The procedure used in this study was the direct messaging to parents/guardians of
adolescents with a goal of engaging them in the health of their adolescent children, by bringing
their awareness to the need and importance of adolescent immunizations. The authors stated that
their health intervention had an overall 25.5% rate of effectiveness (S25). In the Discussion
section of the article, the factors that played to this effectiveness include the utilization of
cellphones for text messaging, as well as ensuring that parents/guardians received multiple text
messages directly, which ushered them to respond to the messages concerning adolescent
immunizations reminders. One of the strengths of this study, as the authors stated, was the
increased engagement and response amongst parents/guardians through text messaging;
however, one of the limitations of the study was the limited means of reaching out to the
parents/guardians of the adolescent subjects. Specifically, other “messaging modalities” (S26)
might have been helpful if incorporated and highlighted in the research study. For instance,
reaching out to parents/guardians through electronic mail.
The authors also pointed out that innovation in technology supported the research study as
the recipients (parents/guardians) are utilizing their electronic devices, where they receive
constant reminders concerning their adolescent children’s healthcare, including their
immunizations. Overall, the methods utilized in this research study show that one of the practical
and successful ways in spreading health awareness and educating communities of diverse
background and status is through direct text messaging- a successful intervention.

ADOLESCENT IMMUNIZATION PROPOSAL 13
Outline
I. Introduction (Program Proposal)
a. Social Assessment
b. Need Statement
i. Epidemiology of Target Population (Adolescent and Parents- knowledge)
ii. Goals, Objectives and Outcomes
c. Epidemiological Assessment
i. Health Objectives and Goals for Target Population
II. Literature Review
a. Theory
i. Theoretical Framework
b. Behavioral and Environmental Factors
c. Health Behavior Factors
i. Predisposing
ii. Enabling
iii. Reinforcing
iv. Administrative and Policy Assessment
III. Methodology (Research Design)
a. Measurement Procedure
b. Sampling
c. Implementation
i. Setting
d. Instruments
e. Data Analysis
f. Ethical Consideration
g. Evaluation and Assessment
h. Strengths and Limitations
i. Conclusion
IV. References
V. Appendix
Meningococcal disease is caused by bacteria Neisseria meningitidis (CDC, 2018). The
bacteria can lead to a higher rate of carrying the Invasive Meningococcal Disease (IMD). This
can cause an infection of the lining of the brain, spinal cord, blood (CDC, 2018). There are 13
identified types of N. meningitidis, referred to as serogroups, but only serogroups A, B, C, W-

ADOLESCENT IMMUNIZATION PROPOSAL 14
135, and Y are known to cause meningococcal disease worldwide (CDC 2018; NFID, 2010).
Serogroups B, C, and Y are responsible for Meningococcal disease cases in the U.S. (NFID,
2010). Serogroup B largely affects infants, and serogroups C and Y are common in adolescents
and young adults. Serogroup Y is most common in people age 65 and older (NFID, 2010). IMD
can spread from person to person through close and prolonged contact such as coughing, and
kissing. It can also spread among those living in the same household (CDC, 2018). Meningitis,
even when treated kills 10 through 15 out of 100 people (CDC, 2018). In addition, for those who
do survive from the disease, 10 through 20 out of 100 people will suffer disabilities such as
hearing loss, brain damage, kidney damage, amputations, and nervous system problems (CDC,
2018).
In order to prevent the transmission and spread of the disease, obtaining vaccinations is
critical. Two meningococcal vaccines are available in the U.S. (NFID, 2010). The first is a
meningococcal conjugate vaccine, MCV4 or Meningococcal ACWY (MenACWY), and was
developed in 2005 (CDC, 2018; NFID, 2010). MenACWY vaccine can help prevent
meningococcal disease caused by serogroups A, C, W, and Y (CDC, 2018). The second vaccine
is a meningococcal polysaccharide vaccine (MPSV4), developed in 1981 (NFID, 2010). These
two vaccines protect against four of the five disease-causing strains of meningitis but
MCV4/MenACWY provides protection for a longer period of time (NFID, 2010). Neither
vaccine however, protects against serogroup B disease, which causes meningitis in infants
(NFID, 2010). A different meningococcal vaccine is available to help protect against serogroup
B (CDC, 2018). Bexsero, referred to as GlaxoSmithKline and Trumenba, referred to as Pfizer
were developed in 2014-2015 to help protect against serogroup B (CDC, 2017).

ADOLESCENT IMMUNIZATION PROPOSAL 15
Two doses of MenACWY are recommended for adolescents 11 through 18 years old
(CDC, 2018). The first dose is routinely given at age 11 or 12, with a booster dose given at age
16 (CDC, 2018). Due to the outcomes and consequences of contracting the disease, steps to
decrease its spread is vital for the overall health and wellness of people. In the United States of
America alone, “…approximately 1500 to 3000 cases occur annually, and the annual disease rate
in recent years ranges from 0.9 to 1.5 cases/100,000” (Reisinger, Black, & Stoddard, 2010, p.
587). Essentially, complete doses of Meningococcal vaccination are crucial to decrease, if not
gradually eliminate the disease.
Behavioral risk factors on lack of vaccination include spread of diseases and viruses. In
addition, behavioral risk factors associated with Meningococcal disease include deep or intimate
kissing (Tully et al., 2014). Intimate kissing with multiple partners increases the risk of
transmitting the disease (Tully et al., 2014). The intervention study will emphasize that deep
kissing with multiple partners’ increases risk of transmission (Tully et al., 2014). The study will
also present to adolescents that flu-like illness or hangover can be early stages of meningococcal
sepsis (Tully et al., 2014). According to Reisinger, Black, & Stoddard (2010), “The most
common initial clinical presentation is characterized by nonspecific symptoms that mimic those
of other more common but less serious illnesses, specifically headache, fever, nausea, vomiting,
and malaise” (p. 586). The need for adolescents to become aware of these signs and symptoms
should be preeminent when evaluating and diagnosing the likelihood of acquiring the disease,
with a goal to decrease its transmission.
Sociodemographic and environmental factors such as health care utilization are used as
predictors of adolescent vaccination. Several studies suggest that the association of provider and
appointment type, timely childhood immunizations, and age are influential factors for adolescent

ADOLESCENT IMMUNIZATION PROPOSAL 16
vaccination uptake- gender and geographic location were not associated with vaccination
coverage. The Healthy People 2020 objective is to increase the vaccination coverage of 1 dose of
meningococcal conjugate for adolescents ages 13 through 15 (HHS, 2018). In 2016, only 39% of
adolescents received at least both doses of the MenACWY (Hasten & Pickering, 2017). 82% of
adolescents received at least one dose (Hasten & Pickering, 2017). This infers that adolescents
do not return by age 16 for the second MenACWY dose (Hasten & Pickering, 2017). There was
a 6% increase in adolescents who received at least two doses of the meningococcal conjugate
vaccine series from 2015 to 2016 (Hasten & Pickering, 2017). The two-year intervention aims to
increase adolescents who are vaccinated with at least 2 doses of meningococcal conjugate
vaccine series by 12%.
The target population will be parents and adolescents who utilize School-Based Health
Centers (SBHCs) in Baltimore City. Baltimore City schools consist of over 37,000 middle and
high school students, approximately 90% are minorities, over 55% come from low-income
household, there are 40 middle and high schools and 13 SBHC (MSDE, 2018 & BCPS 2018).
SBHCs provide comprehensive healthcare in locations at or near a primary or secondary
school (School-Based Health Alliance, 2018). SBHC can meet the needs of students and parents
and provide care that helps the population move towards determined healthcare benchmarks
(School-Based Health Alliance, 2018). Van Ravenhorst, et al. (2017) state that adolescents are a
main target group for meningococcal vaccination, not only to protect this age group against IMD,
but also to reduce carriage and induce herd protection in the population, since adolescents
represent the age group with the highest meningococcal carriage prevalence (p. 4754). According
to Coyne-Beasley, Reiter, Liberty, Ford, Miles, & Brewer, N (2013), knowledge and awareness
concerning vaccinations alone are insufficient (p.449). Rather, a more proactive step that would

ADOLESCENT IMMUNIZATION PROPOSAL 17
be beneficial on increasing the receipt of meningococcal vaccination amongst adolescents is the
active engagement of both the parents and healthcare providers- through educating adolescents
with the risks as well as steps to decrease infection and transmission of the disease.
Factors of Importance
The World Health Organization (WHO) estimates that bacterial meningitis is seen
worldwide, but there’s a more prevalent epidemics that affects over 400 million people in 26
countries in Africa from Senegal to Ethiopia (WHO, 2018). Meningococcal meningitis has a
high fatality of up to 50% when it is left untreated, it also has a high frequency for severe
disability of more than 10%. In the U.S. meningitis incidence is at the lowest rate in history
(CDC, 2017). However, age-specific meningitis is on the rise among infants and at a secondary
peak among adolescents and young adults (CDC, 2017). Adolescent meningococcal conjugate
vaccine (MCV4) immunization, when compared to infant immunization, has shown suboptimal
vaccination coverage in countries with high availability of vaccination resources; the United
States being at 80% in 2016 (Wang, Chen, Ratcliffe, Afzali, Giles, & Marshall, 2017).
Predisposing Factors for Evidence-Based Practice
The predisposing factors that affect adolescent meningococcal vaccination rates include a
gap in knowledge, attitude and practice of parents on the importance of vaccines (Cohen &
Head, 2014; Gargano et. al., 2013-2015; Wang, Chen, Ratcliffe, Afzali, Giles, & Marshall,
2017). A study of parental knowledge, attitude and practice about adolescent vaccines was
conducted in 21 in-depth interviews with parents of 11–18-year-old in rural Appalachia
Kentucky (Cohen & Head, 2014). The study conducted by Cohen & Head (2014) resulted in
three conclusions:
1. Parents’ had different levels of knowledge regarding vaccines.

ADOLESCENT IMMUNIZATION PROPOSAL 18
2. Parents’ who had positive attitudes regarding vaccines were more likely to
get their child vaccinated.
3. Opinion leaders such as local health department nurses were an important
and reliable source of information as opposed to the federal or state
government. They helped to reinforce the benefits of vaccines, despite the
normative beliefs of some parents who were against vaccines.
The study revealed that the parental gap in knowledge about vaccines included
misunderstanding about how vaccines work, along with the false belief that vaccines were live
viruses injected into a person (Cohen & Head, 2014). Other misunderstandings included the
belief that vaccines could make people sick (Cohen & Head, 2014). Parents also “did not want to
‘force’ their adolescent to receive additional medicines or vaccinations that were not required”
(Cohen & Head, 2014).
The absence in knowledge and awareness of Meningococcal disease and meningococcal
conjugate vaccine (MCV4), by adolescents and their parents, are a common reason as to why
adolescents lack adherence to the recommended booster dose that is MCV4 (Gargano et.al.,
2013). A study was done by Gargano et.al. (2013) in a county in east Georgia comprised of
urban and rural schools, and a mostly low-income minority population with one of the lowest
uptake of Meningococcal vaccination among adolescents in the United States. The study found
that parent’s perception of child's susceptibility to disease contraction correlates with a positive
attitude towards vaccination; inversely higher parental perception of control on preventative
measures, such as child’s environment and safety, was more closely associated with parent’s
likelihood of questioning the necessity, effectiveness, and safety of immunization for their child
(Gargano et. al. 2013). Several barriers were found to be associated with this trend in lack of

ADOLESCENT IMMUNIZATION PROPOSAL 19
adolescent immunization adherence including; lack of knowledge and awareness of vaccination
recommendation in parents and patients, concerns with side effects, low participation in regular
preventative health visits, and unawareness of vaccination schedules. (Wang, Chen, Ratcliffe,
Afzali, Giles, & Marshall, 2017).
An updated survey was conducted in 2015 and found the most common reasons parents
of this population did not choose to vaccinate is due concern of whether their child may become
ill from vaccination (65%), concerns with the possible side effects of MCV4 (62.1%), and finally
stating that their child, “does not need” vaccination (58.6%) (Gargano et.al. 2013). Further
research conducted by Gargano et.al, (2015) concluded 33% of parents reasoning for not
vaccinating with MCV4 included child’s fear of needles (Gargano et.al, 2015).
Further research has proven immunization recommendation and proper education on
immunization through primary care practitioners is a heavily influential source for immunization
acceptance among parents of adolescents. Gargano et.al (2013) found the top reason parents
made the decision to vaccinate their adolescents with is due to a recommendation from a family
physician (Gargano et.al. 2013). Further research founds physician recommendation tends to
positive reinforcement on parents belief and acceptance of vaccinations, additionally
recommendation for MCV4 by a physician was associated with higher uptake and “intent to
receive” decision by parents of adolescents (Gargano et.al. 2013)
Behavioral Factors for Evidence Based Practice
Factors of importance help determine the implementation, assessment, and outcome of a
program and/or intervention. Research studies show that the engagement of parents of adolescent
children, the availability of health education materials, and social marketing are related to the

ADOLESCENT IMMUNIZATION PROPOSAL 20
receipt of adolescent immunizations- as behavioral and environmental factors of importance
(Dempsey & Zimet, 2015).
The engagement (participation) of parents of adolescent children (parent intervention)
plays an immense role on the receipt of adolescent immunizations. For instance, regarding a text
message intervention, “After controlling for variations in insurance and intervention
implementation, adolescents of the 124 parents enrolled in the text messaging program had
approximately two times the odds of receiving HPV doses on time when compared with
controls” (Dempsey & Zimet, 2015, p. S446). Parents’ participation makes a difference- by
increasing the likelihood of receiving the recommended immunizations for adolescents.
As for the impact of the availability of health education materials (practice intervention)
in relation to receiving the recommended adolescent immunizations, Dempsey & Zimet (2015)
state, “Web-based social media can play a powerful role in mediating vaccination intentions and
decisions.” (p. S447). GoHealthyGirls, a website focusing on the significance of obtaining
immunizations to prevent infections and diseases is an example of the successful impact of the
delivery of health education materials. According to Dempsey & Zimet (2015), in reference to
GoHealthyGirls, “ Beta-testing of this multimedia website among a diverse set of 63 parents and
their daughters demonstrated that, after viewing the website, parents reported significantly more-
positive attitudes about HPV vaccination and higher perceived risk for HPV infection.” (p.
S447). Hence, the availability of health education materials could be a channel to increase receipt
of adolescent immunizations.
Considered as a “population-level intervention”, social marketing is another plausible
way to reach to adolescents and their families- can be utilized for the promotion and education of
immunization. “Social marketing is a process that applies traditional marketing principles and

ADOLESCENT IMMUNIZATION PROPOSAL 21
techniques to influence target audience behaviors that benefit society as well as the individual”
(Dempsey & Zimet, 2015, p. S447).
Environmental Factors for Evidence-Based Practice
In addition to the research study Dempsey & Zimet (2015) conducted on interventions to
improve adolescent vaccination, the research study Golden et al. (2014) conducted was
specifically on process evaluation of an intervention to increase provision of adolescent vaccines
at school health centers- both studies reveal factors of importance on the receipt of adolescent
immunizations. Golden et al. (2014) included the barriers and hindrances that affect the receipt
of adolescent immunizations such as negative side-effects, limited resources (e.g., lack of
transportation), and finances (p. 625).
The process evaluation of an intervention Golden et. al (2014) conducted was focused on
school health centers. The school communities play a vital role in educating the youth,
specifically in health-related issues as well as in taking part in preventative measures, for
instance, in this case, increased receipt of adolescent immunizations. Golden et al. (2014) state,
“Schools are a promising setting for adolescent vaccination because teens spend significant time
there, and schools enforce immunization requirements” (p. 625). As a prime location for health
education and promotion, school health centers can become a channel for adolescents and their
parents to increase their knowledge on the significance of obtaining recommended
immunizations, to achieve optimal health and wellness.
Golden et al. (2014) state, “…many parents are receptive to the school-located delivery
of adolescent vaccinations, with even higher acceptability among families whose children have
not recently seen a doctor.” (p. 626). However, this finding alone is not sufficient to increase
receipt of adolescent immunization. It is critical to further understand the factors (environmental)

ADOLESCENT IMMUNIZATION PROPOSAL 22
that come into play when delivering adolescent immunization at school health centers. Golden et
al. (2014) revealed that “SHCs face two key challenges to adolescent vaccine delivery: parental
consent for immunization and expanding vaccine programs with limited staff resources” (p.626).
Overcoming these challenges through the utilization of interventions and/or programs might be
helpful.
Specifically, in order to tackle these challenges at school health centers, Golden et al.
(2014) focused on incorporating the aspect of process evaluation which, “…investigates how a
program is executed in order to assess and improve implementation” (p. 626). As for the
procedure, Golden et. al (2014) “created a vaccine information packet” including materials such
as flyers and consent forms translated in the Spanish language for speakers of Spanish (p. 626),
all with a goal to increase knowledge and awareness of the importance of adolescent
immunizations. Through the process evaluation of a low-cost intervention, Golden et al. (2014)
found that “Parents indicated the intervention materials were clear and persuasive and provided
reminders about adolescent vaccinations and information about the SHC vaccination program”
(p. 629). Essentially, through parental engagement, availability of health education materials
(immunization) electronically, and access to resources such as school health centers can help
increase the receipt of adolescent immunizations- as primary factors of importance.
Predisposing, behavioral and environmental factors are a few of the factors that influence
adolescent vaccination rates. The focus of the two-year intervention will be addressing
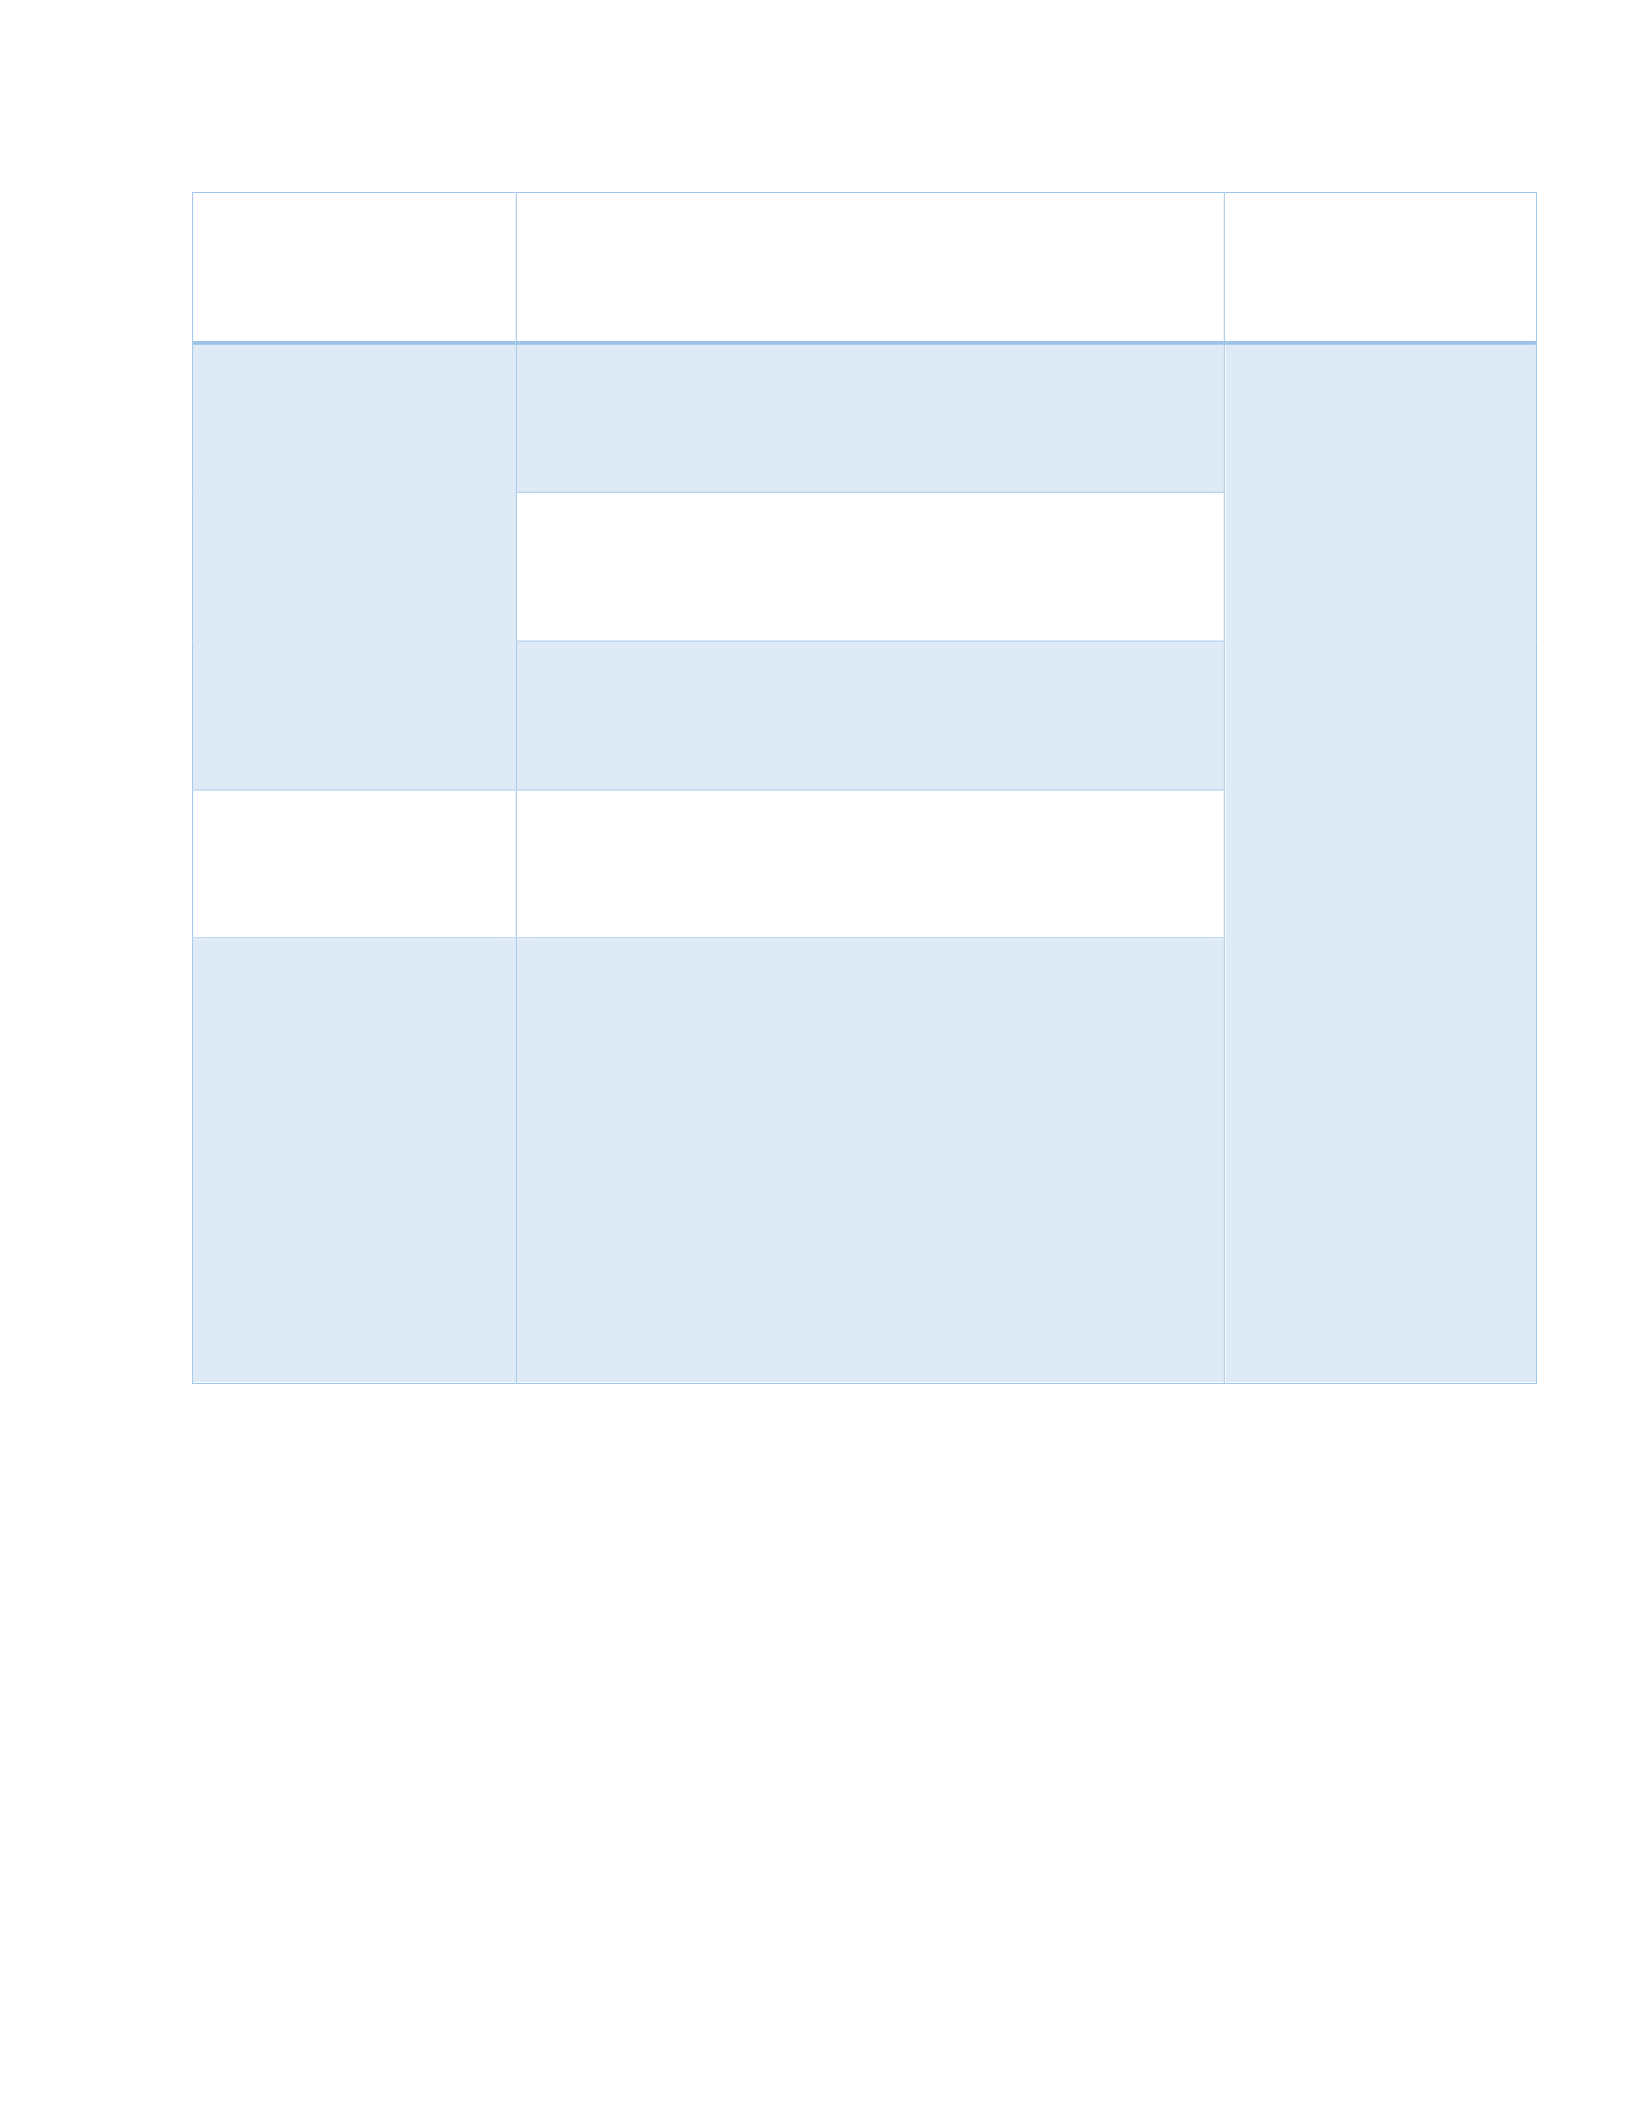
predisposing factors as shown in Table 1, to adolescent meningococcal vaccine acceptance.
Predisposing factors must first be addressed before enabling, reinforcing, behavioral and
environmental factors can be addressed.
Table 1: Factors that affect adolescent vaccine acceptance
ADOLESCENT IMMUNIZATION PROPOSAL 23
Factors of
Importance
Type of Factor
Theory
Predisposing
Lack of knowledge of parents & adolescent about
the meningitis disease and its vaccines.
The Health
Belief Model
(HBM)
Theory of
Reasoned
Action
(TRA)/
Theory of
Planned
Behavior
(TPB)
Social
Ecological
Model
The attitude of parents & adolescent about the
meningitis disease and vaccines.
The practice of adolescent in completing the
meningitis vaccine series.
Behavioral
Non-traditional ways like using social marketing
influence target audience behaviors
Environmental
Limited resources (e.g., lack of transportation), and
finances.
Theories
The Health Belief Model
The health behavior is a conceptual layout of health behavior that’s purpose is to entice
behavior change through the self-efficacy of an individual. This model is geared towards four

ADOLESCENT IMMUNIZATION PROPOSAL 24
levels of contemplation, on an individual basis, that determines whether behavior change occur;
these factors have perceived the risk of contracting illness, the perception of its severity if
contracted, perceived limitations and benefits to the behavior change. (Green & Murphy, 2014).
This theory has been utilized often in order to research barriers in vaccination uptake among
adolescents.
Those adolescents whose parents do not see a perceived risk of their child contracting
Meningococcal disease tend to neglect or turn down opportunities to immunize their children
with MCV4 vaccine during the recommended timeslot. Parents may not have sufficient or
correct information about the susceptibility or severity of this illness, and family physicians may
have the most influential determinant that could bridge the gap of adolescent immunization
discrepancy in the U.S. (Gargano et al., 2013). Unfortunately, studies have also shown that
adolescent population are also less likely than children to adhere to recommended frequencies of
health visits, so the opportunity for primary care physicians to provide knowledge on the risks
and susceptibility adolescents have to Meningococcal virus to both patients and their families
(Clark, Cowan, Stokley, Bilukha,& Davis, 2006).
This particular research conducted by Clark, Cowan, Stokley, Bilukha,& Davis (2006)
recommended that adolescents, during entry to middle school, and their parents be informed of
the MCV4 vaccination because of the likelihood of compliance. At this time the adolescents and
their primary care practitioners’ early intervention can shape both adolescent and their families
perceived benefits of MCV4 immunization while also addressing obstacles and barriers
including future health behaviors that may lessen the frequency of the adolescent accessing this
vaccine if the child or their family decides to put off this particular vaccination. For instance,
insurance coverage/ reimbursement and less frequent health visits as teens that may cause missed

ADOLESCENT IMMUNIZATION PROPOSAL 25
opportunity for being vaccinated for the meningococcal disease. (Clark, Cowan, Stokley,
Bilukha, & Davis, 2006)
The cue to action, in this case, is for parents taking the opportunity to make
recommended primary care health visits with their child around middle school age in order for
the primary care physician to have the opportunity to correctly inform both parties about MCV4
immunization simultaneously and while informing these adolescents earlier so. Finally, both
patient and their families will have the ability to communicate their concerns and questions about
immunization with their PCP and so the health care professional can clarify misconceived
notions they may have about immunization. A study conducted that surveyed 587 physicians on
adolescent patients frequency of visit and adolescent willingness to adhere to MCV4
immunization. The study implementing a fact sheet, from the Advisory Committee on
Immunization Practices (ACIP), about MCV4 immunization to ease physician recommendation
in conversation about vaccination. Results of this study found physician an approach of “best-fit”
worked best as organic conversations about vaccination with adolescence proved to show the
most adolescent compliance with the MCV4 recommendation. (Clark, Cowan, Stokley, Bilukha,
& Davis, 2006)
Theory of Reasoned Action/Planned Behavior
TRA/TPB is used to understand how social norms and environmental influences affect
behavior (Cohen & Head, 2014). Gargano et al., (2014) utilized the Health Belief Model (HBM)
and Theory of Reasoned Action/Planned Behavior (TRA/TPB) to guide the intervention
curriculum and educational material development for parents, teachers, and adolescents. The
intervention program involved three stages:

ADOLESCENT IMMUNIZATION PROPOSAL 26
Stage 1: Intervention Development: Preliminary research for the creation of a parent
brochure consisting of 8 pages of information regarding vaccines by utilizing focus groups.
(Gargano et al., 2014).
Stage 2: Preliminary Research: Teacher-Delivered: An adolescent curriculum was
developed using focus groups to determine current knowledge and attitude about vaccines
(Gargano et al., 2014).
Stage 3: Teacher-Delivered Adolescent Curriculum Development: A pilot test and
mock training session were conducted on the finalized curriculum consisting of
PowerPoint presentation, a video on how vaccines work, a disease-spread activity, pre
and posttest, and a car racing PowerPoint game (Gargano et al., 2014).
An evaluation of the first year identified “parents, knowledge, perceived susceptibility,
perceived barriers to vaccination, social norms, and concerns about vaccine safety as important
predictors of vaccine acceptance” (Gargano et al., 2014, p. 557). In addition, the study also found
that “adolescents perceived susceptibility to infection, perceived barriers to vaccination, and
perceived benefit of vaccines …were important predictors of vaccination” (Gargano et al., 2014,
p.557). The first year evaluation of the program about parental opinions to the brochure revealed
that 97% of parents understood the brochure and 93% believed that the brochure increased their
knowledge (Gargano et al., 2014). An evaluation of the teacher delivered adolescent curriculum
revealed that out 667 middle schoolers there was an increase in students’ knowledge of the four
recommended teen vaccines from 21% to 66.4% in regards to the pre and posttest (Gargano et
al., 2014). Out of 401 high schoolers, the scores increased from 38.7% to 67.6% (Gargano et al.,
2014).

ADOLESCENT IMMUNIZATION PROPOSAL 27
A baseline survey revealed that most of the adolescents had a positive attitude about
vaccines (Gargano et al., 2014). A pre and posttest survey score on middle school students
revealed an increase from 78.6% to 87.4% where they responded whether they believed vaccines
could prevent people from getting sick (Gargano et al., 2014). The survey also revealed an
increase in middle school students from 70.0% to 82.9%, who were interested in getting the
adolescent vaccinations (Gargano et al., 2014). The number of high school from students
increased from 77.3% to 84.8% %, who were also interested in getting the adolescent
vaccinations (Gargano et al., 2014). TRA/TPB constructs include “knowledge, beliefs, attitudes,
norms, personal agency, environmental constraints, and behavioral intention,” all of which are
important when promoting preventive health behavior changes (Cohen & Head, 2014).
Socio-Ecological Model
The Socio-Ecological model is centered on the understanding that there are several
determinants that contribute to individuals health behavior, including; intrapersonal,
interpersonal, institutional, community, and public policy influencers (NIH, 2012). The root of
this theory is the individual and the determinants of behavior is dependent on “multilevel” cohort
of influential factors that influence health behavior (NIH, 2012). School located vaccination
clinics (SLVC) have been developed in the community targeted to increase adolescent
immunization numbers, including uptake of MCV4. These school-based programs increased
adolescent accessibility to vaccination in a school setting while increasing vaccination
acceptability by parents and child (Gargano et al., 2015). Data was gathered through parent
surveys of 6 middle schools and 5 high schools in Georgia, this survey was given to parents post
a 3 level intervention cycle. First, Parent only immunization education initiative, a parent and
student education class, and finally a 2-3 day immunization curriculum for students (Gargano et

ADOLESCENT IMMUNIZATION PROPOSAL 28
al., 2014). This study found parents that had not had their adolescent vaccinated with the MCV4
vaccine but were open to having their child vaccinated had three times the likelihood of allowing
their child to participate in SLVC for MCV4 vaccine than parents who had no intention of
having their child vaccinated (Gargano et al., 2015).
From an intralevel perspective, this SLVC program could positively influence attitudes
towards vaccination, specifically MCV4, for adolescents and their families while also providing
important immunization knowledge regarding risk and susceptibility. Additionally, SLVC ’s
removing barriers of accessibility for certain groups of adolescents that may have insurance or
transportation barriers (Gargano et al., 2014). From an interpersonal standpoint, parents have the
opportunity to relay correct immunization knowledge about MCV4 and debunk incorrect
preconceived notions about immunization by members within social network, and outside of
their social network. From the perspective of an institutional level, immunization education
provided to adolescents and their parent from school with reinforcing recommendation from their
family care physician could greatly influence parent and adolescents acceptance of MCV4 while
also influencing SLVC participation (Gargano et al., 2015) (Gargano et.al., 2014).
On the community level, the exchange of correct immunization information rooted from
SLVC program could heighten community awareness of the presence Meningococcal disease
and provide a general understanding of the perceived risk of adolescents not being vaccinated
with MCV4 on time (Gargano et al., 2014). From a policy level, SLVC’s mandated in schools
across Georgia would ideally influence acceptance and correct common knowledge across state
jurisdictions inevitably to address the discrepancies in adolescent immunization of
Meningococcal disease which is a common trend for adolescents in the state of Georgia
(Gargano et al., 2014).

ADOLESCENT IMMUNIZATION PROPOSAL 29
Goals and Objectives
The Healthy People 2020 objective is to increase the vaccination coverage of 1 dose
meningococcal conjugate for adolescents ages 13 through 15 (HHS, 2018). In 2016, 39% of
adolescents received both doses of the MenACWY compared to 82% of adolescents who
received one dose (Hasten & Pickering, 2017). There was a 6% increase of adolescents who
received at least two doses of the vaccine series from 2015-2016 (Hasten & Pickering, 2017).
The goal of the two-year intervention is to increase adolescents who complete the meningococcal
conjugate vaccine series by an additional 12% from the 39% recorded in 2016.
Several factors affect the acceptance of adolescent meningitis vaccine. The ones
identified for the two-year intervention study are predisposing factors that consist of knowledge,
attitude, and practice (KAP) gaps of parents and adolescents that influence meningitis vaccine
acceptance. The goal of the two-year intervention is to increase KAP of parents and adolescents
to promote meningitis vaccine acceptance. The first objective is to increase the knowledge of
parents and adolescent about the meningitis disease and its vaccines in Baltimore City within two
years by 65%. Gorgano et al., (2013) revealed knowledge increase of adolescents to be around
65%. The second objective is to improve the attitude of parents and adolescent about the
meningitis vaccine by 80% within two years of the intervention. Gorgano et al., (2013) revealed
that adolescents who believed in getting vaccinate were around 80-90%. The third objective is to
increase the practice of adolescent completing the meningitis vaccine series by 51%, this will be
a 12% increase from the 39% recorded in 2016.
ADOLESCENT IMMUNIZATION PROPOSAL 30
Logic Model
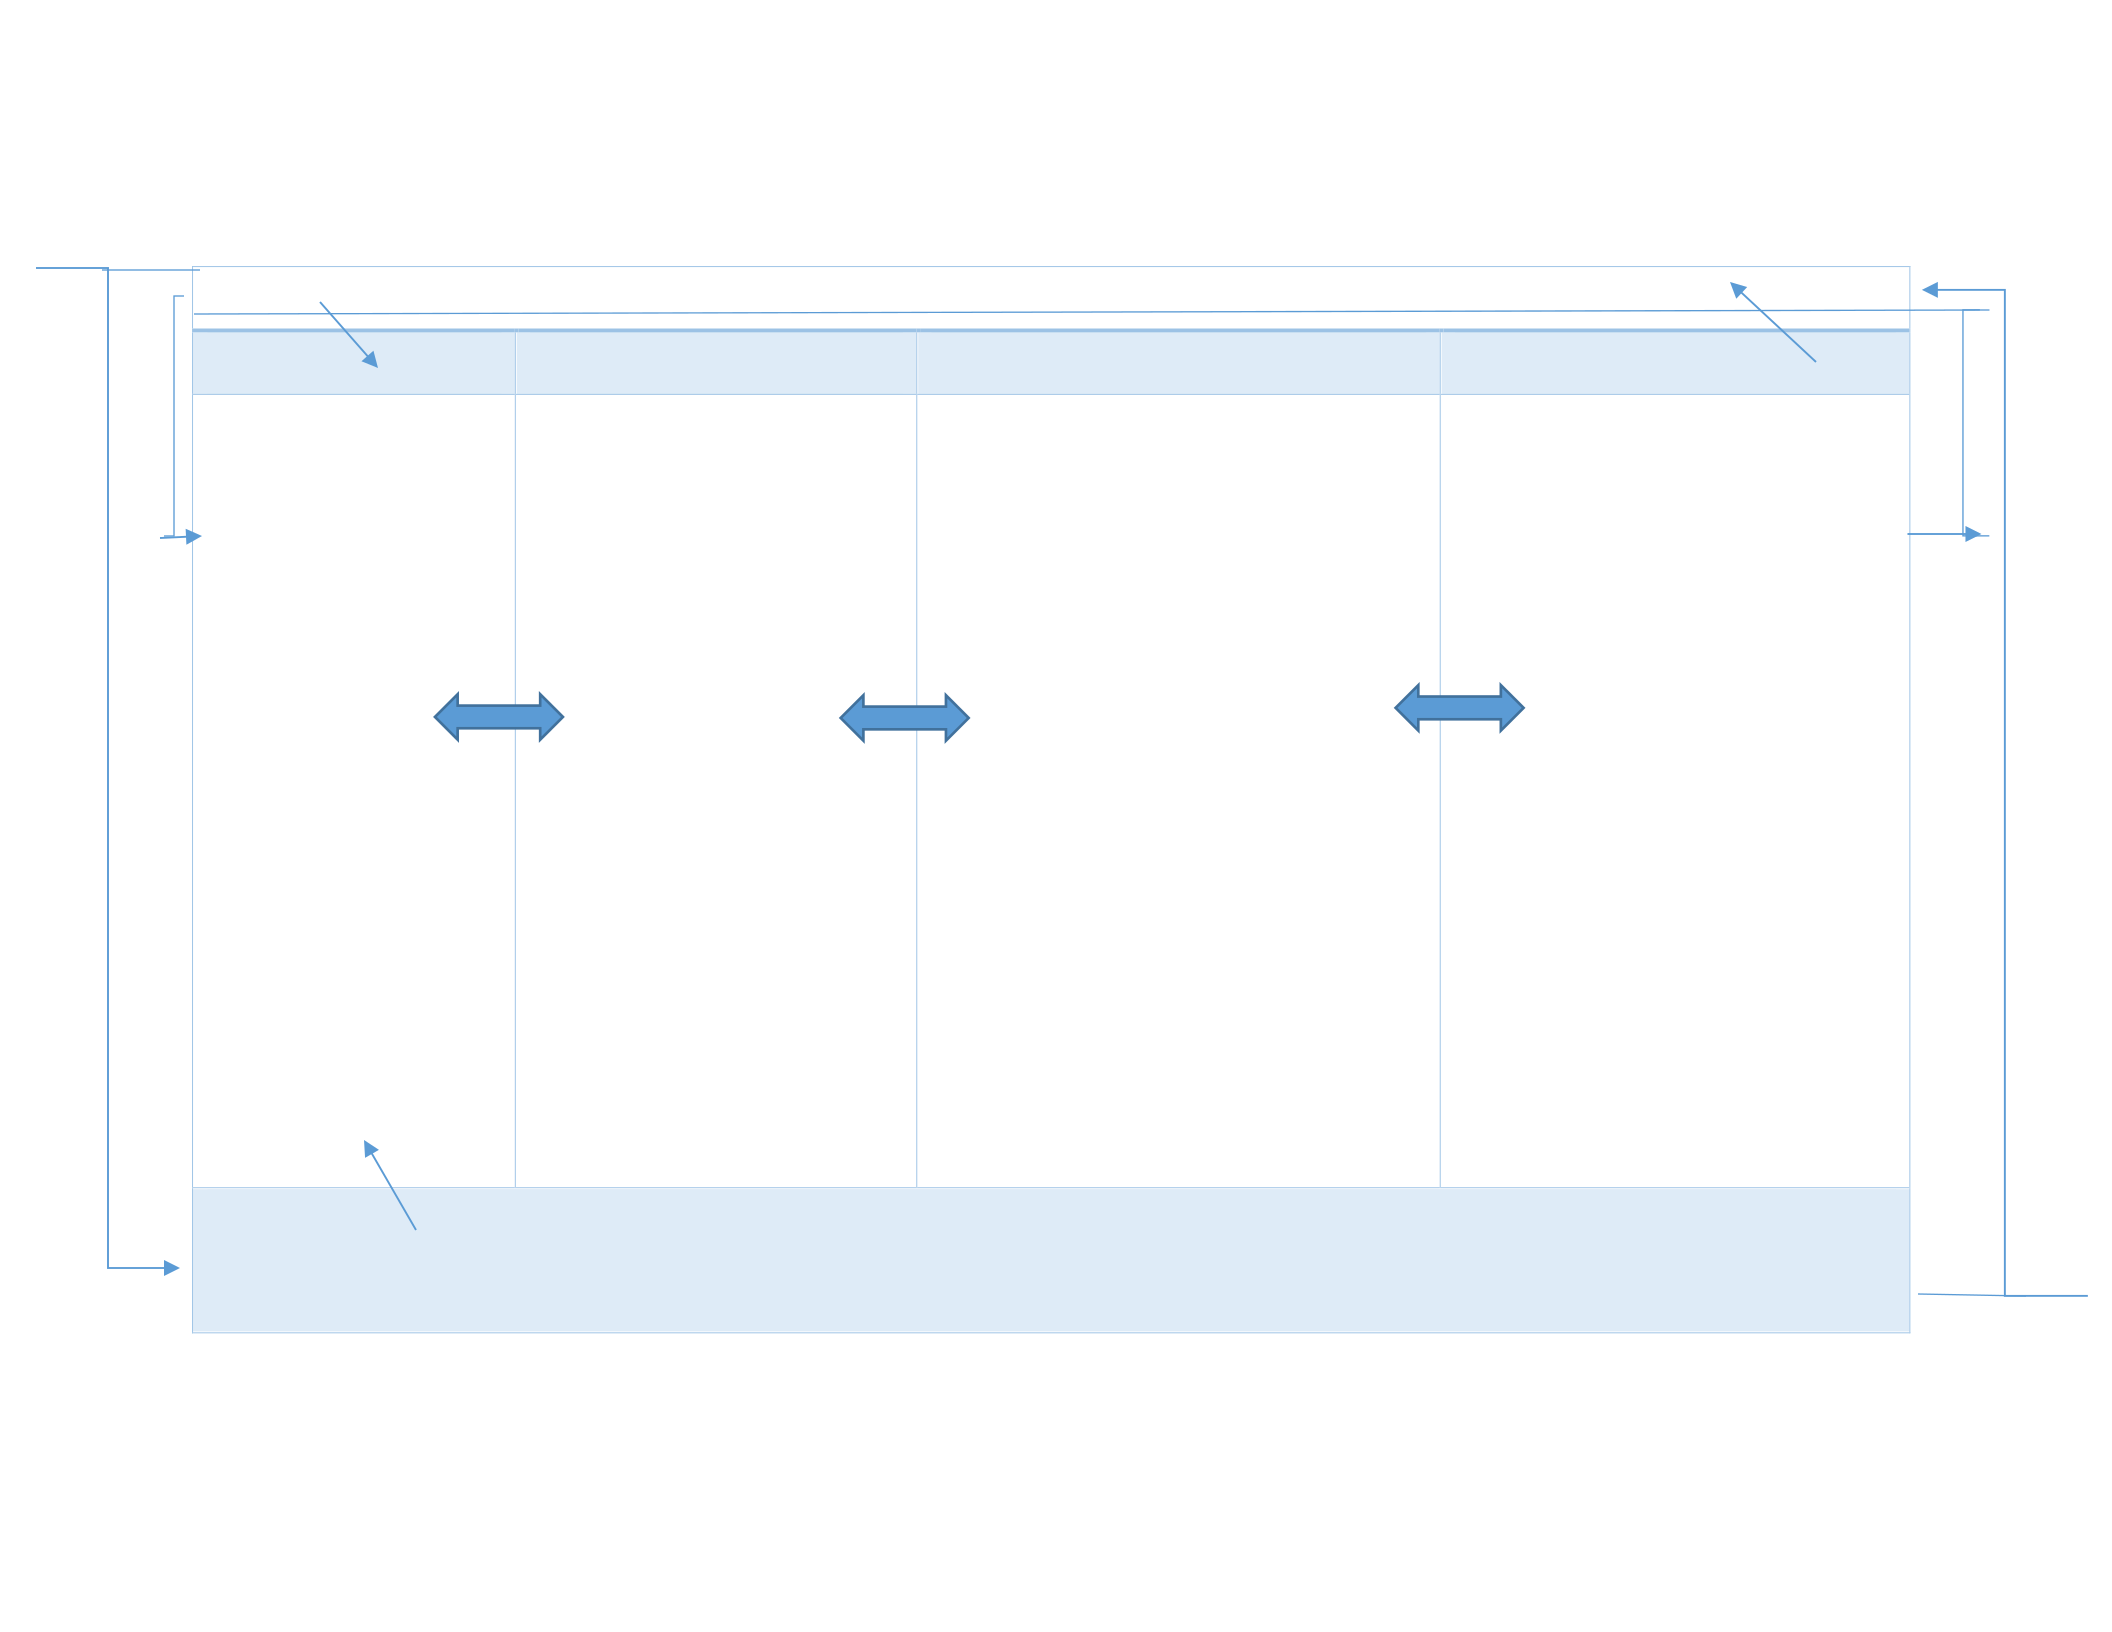
Purpose: To increase adolescents who complete the meningococcal conjugate vaccine series.
Inputs/Resources
Activities
Outputs
Effect
School facility
Staff: Health &
science teachers,
nurse
Skills
Time
Vaccine
curriculum
Technology
Money
MCV4 vaccines
Meetings
Surveys
Curriculum lessons:
vaccines, and health
education
Parent brochures
Parents texts and emails
Training sessions
SBHC nurse, teachers, researchers will
meet with school and parents to finalize
how the two-year study will be conducted.
Researchers, nurse, teachers will all work
towards completion of the study.
Teachers will be trained to deliver lessons.
Students will complete pre and post
surveys.
Parents will receive email/texts on what
students learned. Some text will link to a
brief knowledge & attitude survey.
Parents will receive brochures on vaccine
and meningitis.
Teachers, parents and school nurse will
encourage students to be vaccinated.
Parents will increase knowledge
about meningitis and its vaccine.
Students will increase knowledge
about meningitis and its vaccine.
Parents will improve attitude about
meningitis and its vaccine.
Students will improve attitude
about meningitis and its vaccine.
Students will increase the practice
of meningitis vaccine acceptance.
Context: Age-specific meningitis is at a peak among adolescents. In 2016, only 39% of adolescents completed the meningitis vaccine series. Knowledge,
Attitude, and Practice (KAP) gaps exist among parents and adolescent and negative influences vaccine acceptance.

ADOLESCENT IMMUNIZATION PROPOSAL 31
Program Background
To increase the receipt of adolescent immunization (meningococcal vaccine), the
program intervention will be focusing on adolescents as the target population within school
communities. As a “promising location for immunization interventions” (Salazar et. al, p. 513),
school-based programs can enhance students’ overall health and wellness through preventative
treatment such as the receipt of recommended immunization. In this school-based program
intervention, we will target adolescents, 12- 19 years of age that are currently attending middle
school and high school. Our utmost goal for the program intervention is to increase the receipt of
adolescent immunization. Specifically with adolescents receipt of meningococcal conjugate
vaccine (MCV4) and meningococcal ACWY, as recommended by the Centers for Disease and
Control Prevention.
The program intervention will take place in Baltimore, Maryland. According to the
Baltimore City Health Department (2018), the immunization requirements necessary for middle
school and high school (entrance into 7-11th grade) are one dose of Tetanus, Diphtheria, Pertussis
(Tdap) VIS and one dose of the Meningococcal vaccine. To overcome barriers and hindrances of
obtaining required school immunizations for students, it is necessary to conduct further and in-
depth study of the City of Baltimore; focusing on the residents and their resources (or lack
thereof). With regards to the health of Baltimore, Maryland residents, the Baltimore City Health
Department states, “This reality is compounded by a series of complicated systemic social,
political, economic, and environmental obstacles.” (2018)
In reference to the school environment, Salazar et. al (2016) state, “Given the amount of
time students spend there, the school environment is both an environment for potential disease
transmission and a promising location for immunization interventions.” (p. 513) In order to

ADOLESCENT IMMUNIZATION PROPOSAL 32
increase the rate of adolescents’ receipt of required school immunizations, specifically for
meningococcal vaccine, this program intervention will be conducted within the school
community and environment. The most preeminent goal of the program intervention is that with
the increased receipt of adolescent immunization, the spread of disease will decrease/gradually
eliminated and that each target population (i.e., adolescents) will have access to optimal health
and wellness in the City of Baltimore, Maryland.
The objectives of this two-year school-based program intervention include: increased
parents and guardians’ knowledge and awareness of recommended and required immunization of
adolescents by 65%, enhance and improve the attitudes of parents and guardians’ of adolescents
concerning the receipt of immunization by 80%, complete the meningococcal vaccine series by
51% all within two years. In order for adolescents in the school system in the City of Baltimore
to attend school they need to complete at least one dose of meningococcal vaccine before entry
to the 7th -11th grade (Maryland Department of Health, 2018). The schools chosen for the two
year intervention are School Based Health Centers (SBHC) that adolescents can go to receive
their vaccines. A 2016 news report by The Baltimore Sun reported that Baltimore City schools
have started barring students who have not completed their immunization requirements from
entering schools. With this two year intervention, an area of need can be met in which by
implementing the program schools will be able to get students to meet the vaccine requirement.
While this intervention focuses on meningococcal vaccines, schools can use this opportunity to
get students vaccinated with other required vaccines.

ADOLESCENT IMMUNIZATION PROPOSAL 33
Program Implementation (First and Second Year)
For the implementation of the two-year program intervention, our target population will
be students in 6th-12th grade; these students will be recruited from two School Based Health
Centers (SBHC) in Baltimore, Maryland. There are 19 school-based health centers in Baltimore
City. These centers bring the services of a doctor's office to schools so students avoid health-
related absences and get support to succeed in the classroom. We will be specifically looking at
one that serves middle school students and one that serves high school students. It is possible that
one of the SBHCs will serve elementary and middle school students, in this case only middle
school students will be targeted. None of the 19 SBHC are located in schools that contain both
middle and high school students. Before the start of the program there will be an initial meeting
with the school principal and the SBHC director of the SBHCs we’ve targeted. Their input on
who can best deliver the teacher curriculum and the nurses who can help with logistics on how to
get parental permission for student vaccination while help ensure seamless transition, health
teachers will be encouraged to deliver the curriculum.
Once the two schools and the related health centers are onboard, another meeting with the
identified teachers and health care workers will be conducted. Teachers and the health care
workers will be presented with the curriculum and logistics of the intervention. Teachers will
attend a three day training on curriculum delivery during the summer prior to school starting.
Health care workers will attend on a one day training on logistics, vaccine delivery, parent
consent, and how best to record information on students who get vaccinated. The first year will
focus on a middle school, and the second year will focus on a high school.
Health class in Baltimore City is normally 45 days in the school year (BCPS, 2015).
Depending on if it’s taught in one quarter or a semester using an alternating A day, B day

ADOLESCENT IMMUNIZATION PROPOSAL 34
schedule the vaccine topics can be completed within 7-10 days, leaving the teacher with time to
cover other health topics. Students will take home a flyer to inform parents of the program, a
registration form for the SBHC and a parent/guardian consent form for the program. Students
will receive a $5 gift certificate when they return the signed forms without regard to the parents’
decision. The parents who do not consent to their child being in the program will not have any
recorded information collected on their child, but there child will still benefit from learning about
meningitis and vaccines, since this is a topic that fits under the Personal Health and Wellness
Unit for Health Education Curriculum Analysis Tool (HECAT) which is a more detailed
curriculum of the National Health Education Standard (NHES) being utilized by schools to teach
skill based health education (CDC, 2018). Students whose parents do not consent will not be
required to complete the surveys, however teachers may decide to use it as a performance
analysis strictly for the benefit of the schools. Students whose parents do consent will receive an
additional $5 gift certificate at the end of the program.
A convenience sample of adolescents will go through the two-year intervention, and this
will be from those parents who given their consent. The target for returned signed forms from the
two schools is approximately 100 youth from a sample of 200 youth. Before the start of the
program students will receive an additional flyer to give to their parents on how to download a
seesaw app, which is a student-driven digital portfolio (Seesaw, 2013). Seesaw allows teachers to
add documents that parents can view by downloading the app for free (Seesaw, 2013). This
ensures parents received information of what’s being taught. The app can also be used by
students to show what they know via photos, videos, etc., which can be shared with parents with
the teachers approval (Seesaw, 2013). The teacher can also provide a personal QR code to
parents to view their child’s work (Seesaw, 2013). This tool can be utilized by the teachers even

ADOLESCENT IMMUNIZATION PROPOSAL 35
after the program concludes. Teachers will administer pretest and posttest to students in class
(Appendix 1). Parents will be sent brief pre-test questionnaire (Appendix 2) about meningitis and
its vaccine via the app. Mentioned in the survey will be DO NOT Google any questions. Those
parents who complete the pre-test survey will have their names entered once to win a $50 gift
card at the end of the program. Parent will be sent continuous summary pdfs of the day’s lesson.
After the final lesson, parents will be sent an e- brochure combining all information covered
along with a posttest survey and will receive another entry to win a $50 gift card. All information
to parents will be sent via the app. If there are issues with parents not able to receive information
via the app, they will be sent information via their child and/or mail. The gift card winners will
be decided at the end of the program. There will be four $50 gift cards for the drawing, so up to 4
winners can be chosen, and parents who completed both surveys will have two chances to win.
These will be repeated for the second year. Parents from both schools have two chances to win
four $50 gift cards.
Nurses from the SBHC will administer vaccination to students whose parents consent.
Both meningitis vaccine doses are available to students. The CDC states that the meningococcal
vaccine may be administered during the same visit, along with other recommended vaccines for
their age group. So whether a youth has none, or one of the doses, the meningococcal vaccine
completion series can be done at the same time. When parents and/or youth come to receive the
vaccine, the nurse will reiterate what meningitis is and what the vaccine does, and answer any
questions or concerns of parents and/or adolescents. The same brochure sent to parents after the
final lesson will be available at the SBHC.
The knowledge questionnaire is pulled from GlaxoSmithKline, a British pharmaceutical
company. The company created PowerPoint questions to test meningitis knowledge. The

ADOLESCENT IMMUNIZATION PROPOSAL 36
knowledge question is also pulled from online quiz questions from Meningitis Now, a charity in
England and Wales. The organization works with informing people about meningitis and acting
as a resource. Their question was created online using a survey monkey platform. The questions
are given to teachers for face validity and nurses to ensure content validity. Students and parents
will be given questionnaires at the beginning and end of the intervention to measure Test-retest
reliability. The student curriculum that will be used is from Gargano et al. (2014). Parent and
Teacher–Delivered Intervention on Adolescent Vaccination. It will be slightly modified and
teachers and nurses will help ensure content validity.
Program Evaluation
The pretest and posttest knowledge questionnaire for adolescents contain 15 questions.
The pretest and posttest knowledge questionnaire for parents contain five questions. The pretest
and posttest attitude questionnaire for students include fifteen questions using a typical five-level
Likert Scale which ranges from strongly disagree to strongly agree. A final question is left for
comments about the curriculum, vaccination, surveys or just the program. The pretest and
posttest attitude questionnaire for parents include four questions, and the last question is left for
comments. Each participant’s response is given a final pretest and posttest score number; the
scores are added to give a final score for each individual. The maximum score for the students’
knowledge test is 14, with each correct response question receiving a point. The maximum score
is 25 for the attitude test. The Likert Scale ranges from strongly disagree receives one point to
strongly agree which receives five points. The maximum score for the parent’s knowledge test is
five, with each correct response question receiving a point. The maximum score is 20 for the
parent’s attitude test. Inter-rater/observer reliability will be measured since various teachers will
be delivering the curriculum.

ADOLESCENT IMMUNIZATION PROPOSAL 37
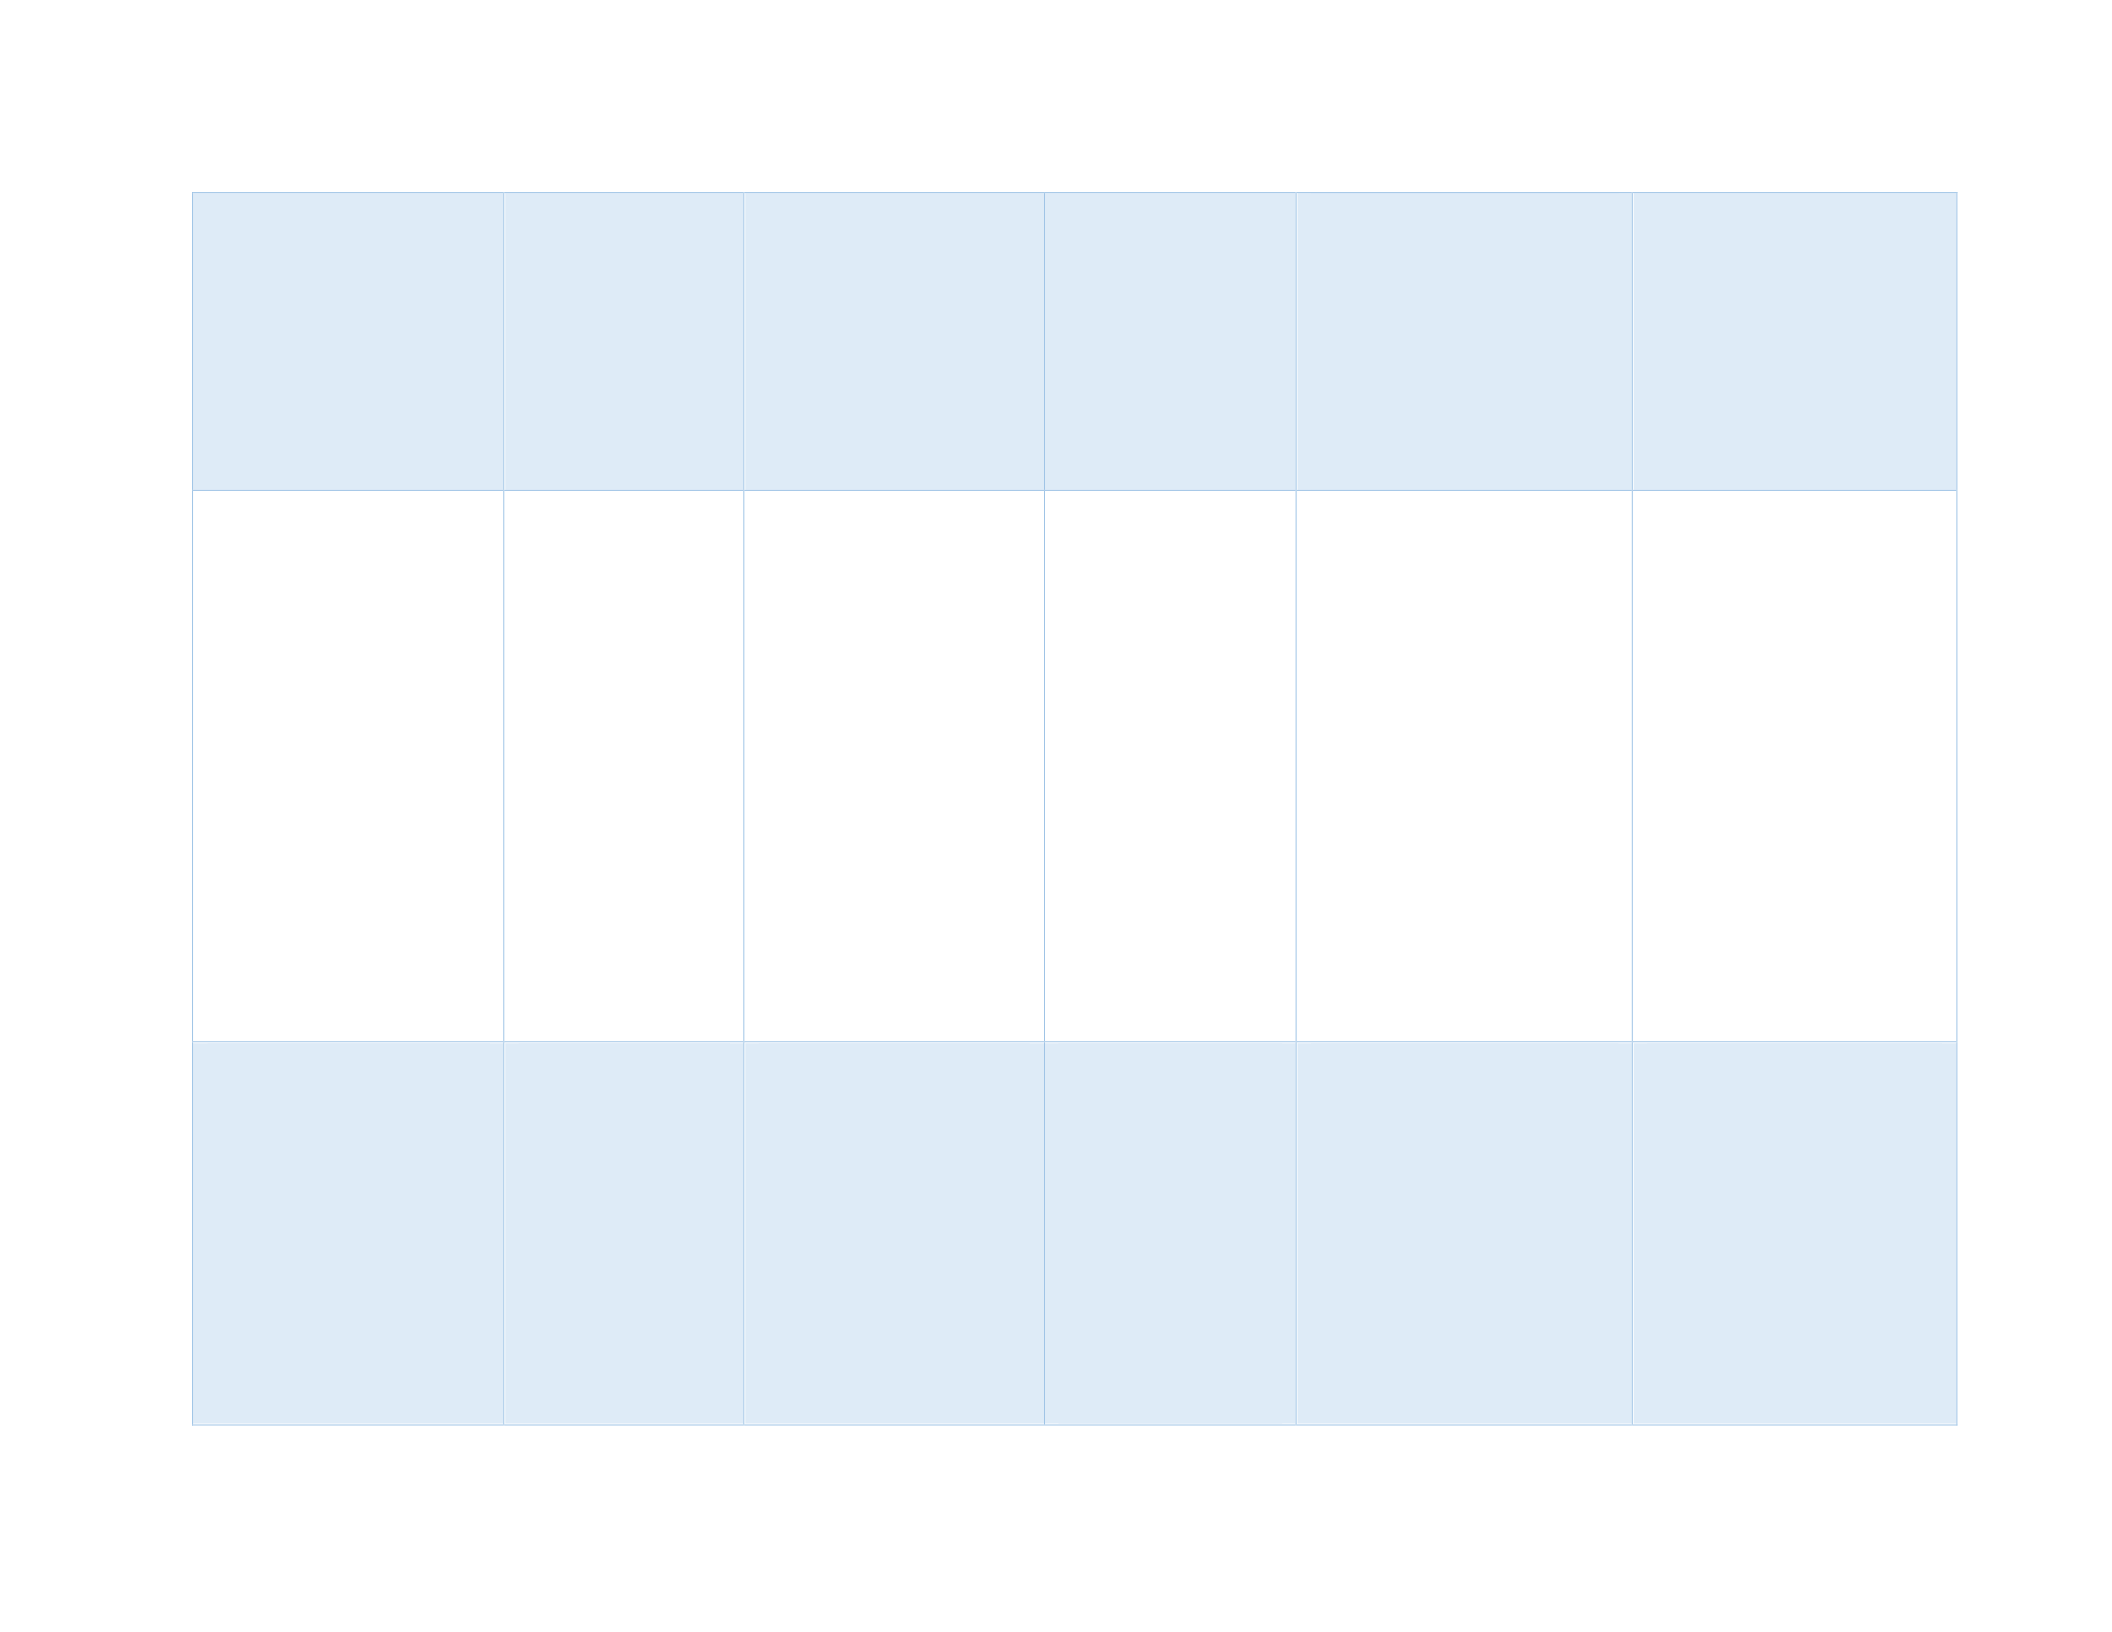
Factor
Type of Factor
Objective
Theory
Implementation
Strategy
Evaluation
The lack of
knowledge of parents
& adolescents about
the meningitis
disease and its
meningococcal
vaccine series.
Predisposing
To increase the
knowledge of
parents and
adolescents about
the meningitis
disease and its
meningococcal
vaccine series within
two years by 65%.
The Health
Belief Model
(HBM)
Year 1: Recruit 6-8
graders from School
Based Health Centers
(SBHC) that serves
middle schoolers.
Teachers will be
trained and teach the
curriculum, administer
pre and posttests to
students.
Parents will receive
documents via seesaw
app along with pre and
posttest about their
knowledge and attitude
about meningitis
vaccine.
Nurses will administer
the vaccine for students
who consent.
Nurses will record the
names of students in
Pre and Post test
ADOLESCENT IMMUNIZATION PROPOSAL 38
the program who
completed the vaccine
series.
Year 2: repeated with
high school students in
9-12 grade.
The
attitude/perception of
parents and
adolescents about the
meningitis disease
and vaccinations.
Predisposing
To improve the
attitude of parents
and adolescents
intention to
vaccinated by 80%
within two years of
the intervention.
The Health
Belief Model
(HBM)
The Theory of
Reasoned Action
(TRA)/ Theory
of Planned
Behavior (TPB)
The Social
Ecological
Model (SEM)
Track progress of
attitude by measuring
feedback from
participants’ intention
to vaccinate in the two-
year program
intervention.
Pre and Post test
The receipt of
adolescent
vaccinations/
completion of the
meningitis vaccine
series (increased
receipt).
Predisposing
To increase the
completion of the
meningitis vaccine
series by 51%.
Theory of
Reasoned Action
(TRA)/ Theory
of Planned
Behavior (TPB)
The Social
Ecological
Model (SEM)
Conduct assessment at
the end of intervention
(e.g., how many
received vaccinations)
of adolescents who
participated in the two-
year program
intervention and who
Number on record of
those students who
were vaccinated.

ADOLESCENT IMMUNIZATION PROPOSAL 39
completed the
vaccination series.

ADOLESCENT IMMUNIZATION PROPOSAL 40
Appendix 1: Student Survey
Knowledge
1. Which of the symptoms below is NOT a symptom of Meningitis?
a) Muscle Pain
b) Hair Loss
c) Cold Hands & Feet
d) Vomiting
e) Stiff Neck
2. How many strains and/or groups of meningitis are there?
a) 2 or less
b) 3
c) 5
d) 6+
There are several strains or 'groups' of meningococcal bacteria such as A, B, C, W, X
and Y
3. Name the two most common causes of bacterial meningitis and/ or septicemia?
a) Meningococcal
b) Pneumococcal
c) Immunococcal
d) Gastrococcal
4. Meningitis is contracted from other people. True or False?
Answer: True
Infections that cause meningitis can be spread through sneezing, coughing, kissing and
sharing utensils, cutlery, and toothbrushes
5. What causes the distinctive rash that does not fade when a glass is rolled over it?
a) Meningitis
b) Septicemia
c) Chickenpox
d) Measles
6. You can’t have meningitis if you don’t have the distinctive rash. True or false?
Answer: False
The distinctive rash associated with meningitis often appears later than other symptoms
or not at all. It is a sign that the disease is advancing quickly, so it is important not to wait
for the rash before seeking help
7. Who is most at risk from meningitis?
a) Babies
b) Young children
c) Adolescents
d) Adults

ADOLESCENT IMMUNIZATION PROPOSAL 41
8. Adolescents and young adults can’t get meningitis. True or false?
Answer: False
The number of meningitis cases peaks again in this age group
9. Vaccination is not as important as there is not a single vaccine to protect against all
strains of meningitis. True or false?
Answer: False
There are several strains or 'groups' of meningococcal bacteria such as A, B, C, W, X,
and Y. Vaccines to help protect against some of these strains are available, so please
speak to a nurse, doctor or pharmacist for further information.
10. What is the main way that doctors treat bacterial meningitis and/ or septicemia?
a) Cold compress
b) Aspirin
c) IV antibiotics
d) Plaster
11. If you suspect someone of having meningitis, what should you do?
a) Nothing
b) Wait 24 hours to see if it gets worse, and then take them to hospital
c) Trust your instincts and seek the nearest medical help
12. What percentage of 15-19-year-olds carry bacteria causing meningitis in the back of their
throat?
a) 10%
b) 0%
c) 50%
d) 25%
13. If someone has become infected with meningitis-causing bacteria, how long does it
usually take for symptoms to develop?
a) 2-4 hours
b) 24 hours
c) 2-10 days
d) 1 month
14. Viral meningitis is more common and less harmful than bacterial meningitis. True or
false?
Answer: True
There is no vaccination or treatment for viral meningitis (except treatment for meningitis
caused by the herpes virus). Bacterial meningitis is of greater concern than viral
meningitis because it is associated with a significant risk of brain damage and death.
Attitude
15. I worry that I may be at risk of getting meningitis
16. I worry that the meningococcal vaccine is not safe to get and have negative side effects
ADOLESCENT IMMUNIZATION PROPOSAL 42
17. I think that getting the meningococcal vaccine is more harmful than not getting it
18. I would get the meningococcal vaccine because it is required by the school, but not my
personal preference
19. I worry that if I receive the meningococcal vaccine series, I would get neurologic
problems
20. Comments:
Appendix 2: Parent Survey
Knowledge
1. How many strains and/or groups of meningitis are there?
a) 2 or less
b) 3
c) 5
d) 6+
There are several strains or 'groups' of meningococcal bacteria such as A, B, C, W, X
and Y
2. What percentage of 15-19-year-olds carry bacteria causing meningitis in the back of their
throat?
e) 10%
a) 0%
b) 50%
c) 25%
3. If someone has become infected with meningitis-causing bacteria, how long does it
usually take for symptoms to develop?
e) 2-4 hours
a) 24 hours
b) 2-10 days
c) 1 month
4. Meningitis is contracted from other people. True or False?
Answer: True
Infections that cause meningitis can be spread through sneezing, coughing, kissing and
sharing utensils, cutlery, and toothbrushes
5. Vaccination is not important as there isn't a single vaccine to protect against all strains of
meningitis. True or false?
Answer: False
There are several strains or 'groups' of meningococcal bacteria such as A, B, C, W, X,
and Y. Vaccines to help protect against some of these strains are available, so please
speak to a nurse, doctor or pharmacist for further information.
Attitude
6. I worry that my child may be at risk of getting meningitis.
a) Strongly agree

ADOLESCENT IMMUNIZATION PROPOSAL 43
b) Agree
c) Neutral
d) Disagree
e) Strongly Disagree
7. I worry that the meningococcal vaccine is not safe for my child, as it may have negative
side effects.
a) Strongly agree
b) Agree
c) Neutral
d) Disagree
e) Strongly Disagree
8. I think that giving my child the meningococcal vaccine is more harmful to him/her than
not giving it.
a) Strongly agree
b) Agree
c) Neutral
d) Disagree
e) Strongly Disagree
9. I would have my child get the meningococcal vaccine because it is required by his/her
school, but not because of personal preference.
a) Strongly agree
b) Agree
c) Neutral
d) Disagree
e) Strongly Disagree
10. Comments:

ADOLESCENT IMMUNIZATION PROPOSAL 44
Program Budget Narrative
The two-year program intervention budget for the school-based immunization intervention will
be $100,000, essentially, $50,000 per year. The following total amounts are projected for the
two-year span of this program:
A. Project Director - Total $ 45,000
The Project Director will dedicate 60% time or 25 hours a week; estimated as $18.75 hourly and
the cost would be $22,500/salary annually over the span of two years. The Project Director is
responsible for the following duties: performing routine program functions, coordinate program
related activities, and oversight of employees in order to make certain program procedures and
benchmarks are met. The Project Director is primarily responsible for data collection, data
evaluation, and reporting duties that may be requires of the funding sources.
B. Trained Healthcare Provider- $10,000
One licensed Healthcare Provider will be available 4 hours a week for 6 calendar months to
administer Vaccinations for these adolescents at their schools, this is since school is not in
session in the summer. Hourly cost for $52 per hour excluding travel expenses. This person will
devote 20-25% on their time providing vaccinations for students at either the middle school or
high school.
C. Part-time Trained Public Health Teacher- $8,000
A trained Public Health Trainer will develop and implement teacher training of Meningococcal
disease for 3 days a month for 6 months/ year to both high school and middle school teachers.
This is a total of 36 individual classes in a two-year span with two- hour classes. This is
approximately $333 per 3/day session, excluding travel expenses.
D. Graduate Assistant (Paid Intern)- $4,800

ADOLESCENT IMMUNIZATION PROPOSAL 45
The Graduate Assistant (GA) will devote 10 hours a week for 6 calendar months to coordinating
activities to volunteers and collecting data. Graduate Assistants will be paid $10.00 per hour.
With direction of project director, this Graduate Assistant will be responsible for mobilizing and
tracking surveys through volunteer, making certain signed consent forms are received for all
participating students and that all program procedures are carried out aligned with protocol.
Student Registration, collection of correct documents, Production of information packets, and
oversight of volunteer staff are primary responsibilities of the Graduate Assistant.
E. Volunteers/Interns- $0 (unpaid)
Volunteers will be hired as needed by staff, and should devote 25% of their time to support of
project supervisor.
Fringe Benefits- $4,384
The Project Director will reserve $4,384 to place towards fringe benefits for 2 calendar years.
FICA standard rate of pay is 8%, FICA taxes will cost $2,184 annually for both the Project
Director and Graduate Assistant. No fringe benefits will be paid for per-diem employees or
volunteers.
Equipment- $10,100
Five laptops will be purchased for teacher training modules, data collection, and logistics costing
$3,000. Appropriate data collection software must also be placed on each laptop costing $1,600,
SPSS at $600 & NVivo at $1,000. Two cellular devices with built in hot spots for portable
internet and follow-up evaluation of parents of participants. Costs associated with cellphones are
approximately $750 for activation and $125 monthly, this will cost $4500 for a span of two-

ADOLESCENT IMMUNIZATION PROPOSAL 46
years. A $1,000 costs will be associated with teacher training tools and student activity materials;
including 3D models of the brain and Spinal cord, and Skin surface.
Printing- $6,500
The cost of $2,000 will be associated with printing two sets each of surveys for both parents and
adolescents; this is for 4,000 individual surveys. The cost for 2,000 consent forms will be printed
at $1,000, and $500 annually. Information pamphlets for parents will cost $3,500 to print for a
total of 2,000 individual pamphlets.
Transportation-$6,200
Volunteers are allotted $15 for travel to and from the two schools. There will be a limit of one
volunteer per school visit per day. A cost of $500 is required for travel reimbursement of
volunteer travel per calendar year, $1,000 for a two- year program. The Graduate Assistant will
also be allotted $15 for travel only to and from schools, this will be limited to 33 trips per
calendar year, totaling $1,000 for the two- year program.
The Health Care Worker and Public Health Teacher are allotted a flat $50 reimbursement for
traveling to schools; Public health teacher is limited to $900 annually, and $1,800 for two years.
The Healthcare Professional is limited to $1,200 annually, or $2,400 for two years. The Program
Director will not be reimbursed for site visits.
Miscellaneous- $5,016
Gift Cards-$1,900
Our target population of participants are 100 adolescents with parental consent from a population
of approximate 200 students. A student receives a visa gift card for $5.00 regardless of consent;
students who complete the program receive an additional $5 gift card for a total of $1,500 will be
ADOLESCENT IMMUNIZATION PROPOSAL 47
the cost for a two-year span. Additionally, four $50 gift card must be purchased for survey
completion the “enter to win” contest for participating parents, for each year of the program for a
total of $400.
Materials /Supplies- $3,116
There will be a cost $ 1,000 annually for printing and stationary tools; printer, ink, paper, folders,
envelopes, pens, staplers, etc. The stationary supplies will utilized by volunteers to develop
information packets for parents. The remaining $1,116 will be used as incidentals that may be
necessary through the duration of the program; for instance additional travel, or stationary supply
replenishment.
Proposed Budget
ITEM
2019
2020
TOTAL
PERSONNEL
$67,800
Project Director
$22,500
$22,500
$45,000
Public Health teacher
$4,000
$4,000
$8,000
Healthcare Provider
$5,000
$5,000
$10,000
Graduate Assistant
$2,400
$2,400
$4,800
Volunteer (s)
$0
$0
$0
TRANSPORTATION
$6,200
Volunteer
$500
$500
$1,000
Graduate Assistant
$500
$500
$1,000
Health Care Provider
$900
$900
$1,800
Public Health Teacher
$1,200
$1,200
$2,400
EQUIPMENT
$10,100
Laptop
$3,000
-
$3,000
Data Collection software
$1,600
-
$1,600
Educational Tools
$1,000
-
$1,000
Mobile Phones
$3,000
$1500
$4,500
FRINGE BENEFITS
$2,192
$2,192
$4,384
PRINTING
$6,500
Survey
$1,000
$1,000
$2,000
Consent Form
$500
$500
$1,000
Pamphlet
$3,500
-
$3,500
Misc. Costs
$5,016
ADOLESCENT IMMUNIZATION PROPOSAL 48
Gift Cards
$950
$950
$1,900
Stationary
$1,000
$1,000
$2,000
Incidental
$558
$558
$1,116
TOTAL COST
$100,000
Program Conclusion
The two-year school-based program intervention that will be taken place in Baltimore,
Maryland from two SBHCs with a target population of students in 6th-12th grade (ages 12-19) has
specific program objectives: 80% increase in knowledge and awareness (parents and
adolescents) of meningococcal vaccine, 70% change in attitude concerning receiving the
meningococcal vaccine series, and 51% completion of vaccination amongst adolescents in these
two participating schools- one middle school and one high school in Baltimore, Maryland. The
program intervention goals are that the parents and/or guardians of the adolescent students will
be educated with the crucial need of meningococcal vaccine and the spread of its disease, so that
they can take preventative steps (attitude) to combat the disease and promote health and wellness
within their community. With a budget of $100,000 ($50,000 per year) for the two-year program
intervention to allocate for planning, implementation, and utilization of resources, the utmost
goal is that adolescents who will be participating in the intervention will complete necessary and
required vaccinations to achieve optimal health and wellness.
ADOLESCENT IMMUNIZATION PROPOSAL 49
References
Baltimore City Public Schools (BCPS). (2018). City Schools at a Glance. Baltimore City Public
Schools (BCPS). Retrieved from
https://www.baltimorecityschools.org/about/by_the_numbers
Baltimore City Health Department (BCHD). (2018). Vaccine Requirements for Children
Enrolled in Preschool Programs and in Schools. Maryland School Year 2018-2019.
Retrieved from:
https://health.baltimorecity.gov/sites/default/files/health/attachments/MDH%20PreK%20a
nd%20School%20Vaccine%20Requirements%20SY%202018-19.pdf
Baltimore City Health Department (BCHD). (2017, March). State of Health in Baltimore: White
Paper 2017. Retrieved from: https://health.baltimorecity.gov/state-health-baltimore-
winter-2016/state-health-baltimore-white-paper-2017
Baltimore City Public Schools (BCPS). (2015). Great Kids, Great Schools. Health Education.
Retrieved from
https://www.baltimorecityschools.org/cms/lib/MD01001351/Centricity/Domain/6734/FY
15/FY15-HealthEducation-FSF110.pdf
Bar-Shain, D., Stager, M., Leon, J., Kaelber, D., & Runkle, A. (2015). Direct messaging to
parents/guardians to improve adolescent immunizations. Journal of Adolescent Health,
56(5), S21-S26. https://doi.org/10.1016/j.jadohealth.2014.11.023
Burns, J.L., Walsh, L.J., & Popovich, J.M. (2010). Continuing Education: Practical Pediatric and
Adolescent Immunization Update. The Journal for Nurse Practitioners, Volume 6, Issue
4.

ADOLESCENT IMMUNIZATION PROPOSAL 50
Centers for Disease Control. (2018). Healthy School: National Health Education Standards. U.S.
Department of Health & Human Services. Retrieved from
https://www.cdc.gov/healthyschools/sher/standards/ &
https://www.cdc.gov/healthyyouth/hecat/index.htm
Centers for Disease Control (CDC). (2018). Meningitis. National Center for Immunization and
Respiratory Diseases, U.S. Department of Health & Human Services. Retrieved from
https://www.cdc.gov/meningitis/index.html
Centers for Disease Control. (2018). U.S. Department of Health & Human Services. Vaccine
Information Statements (VISs): Meningococcal ACWY VIS. Retrieved from
https://www.cdc.gov/vaccines/hcp/vis/vis-statements/mening.html
Centers for Disease Control (CDC). (2017). Vaccines and Preventable Diseases: Meningococcal
Vaccination for Adolescents: Information for Healthcare Professionals. National Center
for Immunization and Respiratory Diseases, U.S. Department of Health & Human
Services. Retrieved from
https://www.cdc.gov/vaccines/vpd/mening/hcp/adolescent- vaccine.html
Centers for Disease Control (CDC). (2017). National Center for Immunization and Respiratory
Diseases, U.S. Department of Health & Human Services.
Meningococcal Disease: Technical and Clinical Information. Retrieved from
https://www.cdc.gov/meningococcal/outbreaks/index.html
Centers for Disease Control (CDC). (2017). U.S. Department of Health & Human Services.
Vaccine Information Statements (VISs): Meningococcal Outbreaks. Retrieved from
https://www.cdc.gov/meningococcal/outbreaks/index.html
Centers for Disease Control (CDC). (2016). National, regional, state, and selected local area

ADOLESCENT IMMUNIZATION PROPOSAL 51
vaccination coverage among adolescents aged 13–17 years—United States, 2015.
MMWR. Morbidity and mortality weekly report, 65.
Clark, S. J., Cowan, A. E., Stokley, S., Bilukha, O., & Davis, M. M. (2006). Physician
perspectives to inform a new recommendation for meningococcal conjugate vaccine
(MCV4). Journal of adolescent health, 39(6), 850-855.
Cohen, E.L. & Head, K.J. (2014). Identifying knowledge, attitude, practice gaps in parental
acceptance of adolescent vaccinations in Appalachian Kentucky: Implications for
communication Interventions. Journal of Communication in Healthcare, VOL. 7, NO. 4.
DOI: 10.1179/1753807614Y.0000000069
Coyne-Beasley, T., Reiter, P., Liberty, A., Ford, C., Miles, D., & Brewer, N. (2013). Awareness
is not enough: the need to increase meningococcal vaccine uptake. Clinical Pediatrics,
52(5), 441-450. https://doi.org/10.1177/0009922813481847
Dempsey, A. F., & Zimet, G. D. (2015). Interventions to Improve Adolescent Vaccination. What
May Work and What Still Needs to Be Tested. American Journal of Preventive Medicine,
49(Supplement 4), S445–S454. https://doi.org/10.1016/j.amepre.2015.04.013
Dempsey, A.F., Maertens, J., Beaty., B and O’Leary, S.T. (2015). Characteristics of users of a
tailored, interactive website for parents and its impact on adolescent vaccination attitudes
and uptake. Adult and Child Center for Outcomes Research and Dissemination
Science (ACCORDS), BMC Res Notes (2015) 8:739. DOI 10.1186/s13104-0151721-8
Federico, S.G., Abrams, L., Everhart, R.M., Melinkovich, P., & Hambidge, S.J. (2010).
Addressing Adolescent Immunization Disparities: A Retrospective Analysis of School-
Based Health Center Immunization Delivery. American Journal of Public Health, Vol
100, No. 9.

ADOLESCENT IMMUNIZATION PROPOSAL 52
Gargano, L. M., Weiss, P., Underwood, N. L., Seib, K., Sales, J. M., Vogt, T. M., & Hughes,
J. M. (2015). School-located vaccination clinics for adolescents: correlates of acceptance
among parents. Journal of community health, 40(4), 660-669.
Gargano, L.M., Herbert, N.L., Painter, J.E., Sales, J.M., Vogt, J.M., Morfaw, C., Jones, L.M.,
Murray, D., DiClemente, R.J., & Hughes, J.M. (2014). Development, Theoretical
Framework, and Evaluation of a Parent and Teacher–Delivered Intervention on
Adolescent Vaccination. Gender & Ethnicity in Adolescent Health, Vol. 15, No. 4 556–
567. DOI: 10.1177/1524839913518222
Gargano, L. M., Herbert, N. L., Painter, J. E., Sales, J. M., Morfaw, C., Rask, K., & Hughes, J.
M. (2013). Impact of a physician recommendation and parental immunization attitudes
on receipt or intention to receive adolescent vaccines. Human vaccines &
immunotherapeutics, 9(12), 2627-2633.
Gowda C., Dong, S., Potter, R.C., Dombkowski, K.J., & Dempsey, A.F. (2013). A Population-
Level Assessment of Factors Associated With Uptake of Adolescent-Targeted Vaccines in
Michigan. Journal of Adolescent Health 53 (2013) 498e505.
Green, E. (2016). Students in Baltimore region without required immunizations will be barred
from schools. The Baltimore Sun. Retrieved from
https://www.baltimoresun.com/news/maryland/education/bs-md-ci-immunizations-
20160914-story.html
Green, E. C., & Murphy, E. (2014). Health belief model. The Wiley Blackwell encyclopedia of
health, illness, behavior, and society, 766-769.
Greenfield, L. S., Page, L. C., Kay, M., Li-Vollmer, M., Breuner, C.C., & Duchin, J.S. (2015).
Original article: Strategies for Increasing Adolescent Immunizations in Diverse Ethnic

ADOLESCENT IMMUNIZATION PROPOSAL 53
Communities. Journal of Adolescent Health, 56, S547-S53.
https://doi.org/10.1016/j.jadohealth.2014.10.274
Hasten, J., & Pickering, L.K. (2017). Coverage rates increase for HPV, Tdap, MenACWY
vaccines. American Academy of Pediatrics. Retrieved from
http://www.aappublications.org/news/2017/11/09/MMWR110917
Healthy People 2020. (2018). Immunization and Infectious Diseases. Office of Disease
Prevention and Health Promotion (ODPHP), U.S. Department of Health and Human
Services. Retrieved from https://www.healthypeople.gov/2020/topics-
objectives/topic/immunization-and-infectious-diseases/objectives &
https://www.healthypeople.gov/node/4657/data_details
Healthy People 2020. (2018). Immunization and Infectious Diseases. Office of Disease
Prevention and Health Promotion (ODPHP), U.S. Department of Health and Human
Services. Retrieved from https://www.healthypeople.gov/2020/topics-
objectives/topic/immunization-and-infectious-diseases/objectives &
Meningococcal Vaccination Improving Rates in Adolescents and Reducing Racial, Ethnic and
Socioeconomic Disparities. (2010). National Foundation of Infectious Disease (NFID).
Retrieved from http://www.nfid.org/idinfo/meningococcal/meningococcal-cta.pdf
How much do you know about meningitis? GlaxoSmithKline, May 2017, GSK group of
companies. Retrieved from https://tacklemeningitis.org/files/downloads/Tackle-
Meningitis-awareness-schools-quiz.pdf
Maryland Department of Health. (2018). Vaccine Requirements For Children. Center for
Immunization. Retrieved from

ADOLESCENT IMMUNIZATION PROPOSAL 54
https://health.baltimorecity.gov/sites/default/files/health/attachments/MDH%20PreK%20
and%20School%20Vaccine%20Requirements%20SY%202018-19.pdf
Maryland State Department of Education (MSDE). (2018). Maryland School-Based Health
Center Programs – Contact Information for Fiscal Year.2019(FY19). Maryland State
Department of Education.
http://marylandpublicschools.org/about/Documents/DSFSS/SSSP/SBHC/SBHCContactL
istFY19.pdf
Meningitis Now: Meningitis quiz #1. Meningitis Now, Fern House, Bath Road, Stroud,
Gloucestershire GL5 3TJ, United Kingdom. Retrieved from
https://www.meningitisnow.org/meningitis-explained/what-is-meningitis/test-your-
knowledge/
Meningitis Now: Meningitis quiz #2. Meningitis Now, Fern House, Bath Road, Stroud,
Gloucestershire GL5 3TJ, United Kingdom. Retrieved from
https://www.meningitisnow.org/meningitis-explained/what-is-meningitis/test-your-
knowledge-again/
National Institute of Health. (2012). The social ecological model as a framework for
determinants of 2009 H1N1 influenza vaccine uptake in the United States. Health
Education & Behavior, 39(2), 229-243.
Reisinger, K., Black, S., & Stoddard, J. (2010). Optimizing Protection Against Meningococcal
Disease. Clinical Pediatrics, 49(6), 586. Retrieved from http://proxy-
tu.researchport.umd.edu/login?ins=tu&url=http://search.ebscohost.com/login.aspx?direct=
true&db=edb&AN=51197185&site=eds-live&scope=site
ADOLESCENT IMMUNIZATION PROPOSAL 55
Salazar, K., Seib, K., Underwood, N., Gargano, L., Sales, J., Diclemente, R., Murray, D.,
Morfaw, C., & Hughes, J. (2016, July). Recommendations for Structure and Content
for a School-Based Adolescent Immunization Curriculum. Health Promotion
Practice, 17(4), 512-520. htttps://doi.org/10.1177/1524839915627458
Salmon, D.A., Dudley, M.Z., Glanz, J.M., & Omer, S.B. (2015). Vaccine Hesitancy Causes,
Consequences, and a Call to Action. American Journal of Preventive Medicine and
Elsevier Ltd, 49(6S4): S391–S398.
School-Based Health Alliance. (2018). SBHC Sustainability: What Makes a School-Based
Health Center Sustainable? School-Based Health Alliance. Retrieved from
https://www.sbh4all.org/resources/sbhc-sustainability/
Seesaw. (2013). Seesaw Learning, Inc. https://web.seesaw.me/
Serra, L.C., York, L.J., Balmer, P., & Webber, C. (2018). Review article: Meningococcal Group
A, C, W, and Y Tetanus Toxoid Conjugate Vaccine: A Review of Clinical Data in
Adolescents. Journal of Adolescent Health, 63, 269-279.
https://doi.org/10.1016/j.jadohealth.2018.05.012
Tully, J., Viner, R.M., Coen, P.G., Stuart, J.M., Zambon, M., Peckham, C., Booth, C., Klein, N.,
Kaczmarski, E., & Booy, R. (2006). Risk and protective factors for meningococcal
disease in adolescents: matched cohort study. BMJ. doi:10.1136/bmj.38725.728472.BE
Turner, K. L., DeFrank, J. T., & Brewer, N. T. (2014). Process Evaluation of an Intervention to
Increase Provision of Adolescent Vaccines at School Health Centers. Health Education &
Behavior, 41(6), 625–632.
Van Ravenhorst, M.B., Van Der Klis, F. Van Rooijen, D., Sanders, E., & Berbers, G. (2017).
Adolescent meningococcal serogroup A, W, and Y immune responses following

ADOLESCENT IMMUNIZATION PROPOSAL 56
immunization with quadrivalent meningococcal A, C, W and Y conjugate vaccine: Optimal
age for vaccination. Vaccine, 35(36). 4753-4760.
https://doi.org/10.1016/j.vaccine.2017.06.007
Wang, B., Chen, G., Ratcliffe, J., Afzali, H. H. A., Giles, L., & Marshall, H. (2017). Adolescent
values for immunisation programs in Australia: A discrete choice experiment. PloS one,
12(7), e0181073.
WebMD. (2018). The Meningitis Vaccines: What Parents Should Know. WebMD LLC.
Retrieved from https://www.webmd.com/children/vaccines/meningitis-vaccine-
whatparents-should-know#1
World Health Organization. (2018). Meningococcal meningitis. Retrieved from
http://www.who.int/news-room/fact-sheets/detail/meningococcal-meningitis &
http://www.who.int/gho/epidemic_diseases/meningitis/en/

Concept Paper
Paragraph would be a good format to identify your topic (Adolescent Immunization).
Target population and the specific Healthy People 2020 objective
At least 6 reliable articles- An article can address one or all of the elements below.
o Listed in annotated bibliography style (using APA 7 format)
o Summary of article with a focus on how the article addresses the 4 elements
o Social assessment
o Epidemiological influence information
o Behavioral and environmental factors
o Factors that influence behavior
Predisposing
Enabling
Reinforcing
You also have to identify a source to gather epidemiological data
Outline
https://www.healthypeople.gov/2020/topics-objectives/topic/immunization-and-infectious-
diseases
https://www.healthypeople.gov/2020/topics-objectives/topic/immunization-and-infectious-
diseases/objectives

Running Head: IMMUNIZATION 1
Adolescent Immunization Annotated Bibliography
Name
Institution

IMMUNIZATION 2
Abdullahi, L. H., Kagina, B. M., Ndze, V. N., Hussey, G. D., & Wiysonge, C. S. (2020).
Improving vaccination uptake among adolescents. The Cochrane database of systematic
reviews, 1(1), CD011895. https://doi.org/10.1002/14651858.CD011895.pub2
In this article, Abdullahi et al. (2020) carry out a literature review to evaluate the effects
various interventions have on improving adolescents' immunization rates. This is because
vaccination among adolescents has become an issue of concern due to the suboptimal
vaccination coverage rates. Abdullahi et al. (2020) provide that targeting adolescents has benefits
since it can help identify missed vaccinations, improve body immunity, and create awareness of
new vaccines. In the paper, Abdullahi et al. (2020) cite that adolescents mostly seek physician
care when ill, limiting the opportunity to get information about vaccines. Also, the article
findings provide that vaccination coverage is limited, considering that globally, only 6.1 percent
of adolescent girls received full dose series of HPV vaccine in 2014. However, the data varies
with countries since vaccination rates were higher in high-income countries than in low-income
countries.
The paper provides that the most common barriers to vaccination among adolescents
include predisposing factors such as lack of knowledge about the vaccines, negative attitudes,
and beliefs regarding the vaccines among the adolescents, teachers, parents, and the healthcare
providers. Other factors include financial constraints and poor vaccine delivery infrastructure.
Following the research, Abdullahi et al. (2020) recommend that interventions targeting parents,
adolescent children, and health care providers are required. This includes interventions such as
addressing predisposing factors by improving health education on HPV and other vaccines to
increase knowledge and awareness. Other interventions include the introduction of reinforcing
factors such as financial incentives, mandatory vaccination requirements to improve vaccine

IMMUNIZATION 3
uptake. Also, enabling factors such as reducing out of pocket expenses and introducing a school-
based vaccination strategy can help improve immunization coverage. However, Abdullahi et al.
(2020) provide that these interventions do not provide certainty, and additional research is
required to improve adolescent immunization programs.
Bar-Shain, D., Stager, M., Leon, J., Kaelber, D., & Runkle, A. (2015). Direct messaging to
parents/guardians to improve adolescent immunizations. Journal of Adolescent Health,
56(5), S21-S26. https://doi.org/10.1016/j.jadohealth.2014.11.023
In this article, the authors recommend using direct messaging and mobile technology to
promote adolescent immunizations. According to Bar-Shain et al. (2015), the CDC reports that
adolescent immunization coverage rates are low. For instance, 15 percent of the population had
not received the recommended tetanus, diphtheria, and pertussis vaccine by 2015. In comparison,
26 percent have not received MCV, and 46 and 79 percent of females and males have not
received HPV vaccines. Also, Bar-Shain et al. (2015) provide that the immunization rates of
adolescents below the poverty line are 1 to 10 percent less than those above poverty line. Other
data provided in the article is that racial and ethnic disparities exist in the completion of various
vaccine doses, with African Americans having the lowest rates of immunization completion
compared to Caucasians and Hispanics.
Bar-Shain et al. (2015) provide that direct messaging to parents can engage them in their
adolescent children's health. The direct messaging intervention aims to create awareness of the
need and importance of ensuring their children's immunization. The authors of the article provide
that this intervention showed a 25 percent rate of effectiveness. The health intervention enablers
included the high utilization of cellphones and emphasized that parents respond to the adolescent
immunization messages.

IMMUNIZATION 4
In the paper, Bar-Shain et al. (2015) argue that technology innovation can help support
immunization bid since it could help parents receive constant reminders regarding their
adolescent children's immunization schedule. The messaging technology can also help spread
health awareness and educational messages regarding vaccination and immunization to diverse
communities. Bar-Shain et al. (2015) also provide that text messages are becoming more prolific,
and parents have become more interested in utilizing them to improve their children's health.
Bernstein, H. H., Bocchini, J. A., & Committee on Infectious Diseases (2017). The Need to
Optimize Adolescent Immunization. Official Journal of the American Academy of
Pediatrics, 139(3), e20164186. https://doi.org/10.1542/peds.2016-4186
In this paper, Bernstein et al. (2017) provide that adolescence marks a transition from a
pediatric patient to an adult patient. In this case, this is a time where effective measures for
preventive care can be developed to ensure adolescent children engage in safe behaviors in their
adulthood. In this case, Bernstein et al. (2017) provide that vaccination is a crucial foundation for
preventative care in adolescents. However, various data sources show that despite the expansion
of adolescent immunization schedules in the past decade, the immunization rates lag behind. The
current immunization schedule consists of two doses of meningococcal conjugate vaccines, three
doses of the HPV vaccine, and one dose of diphtheria, tetanus, and pertussis. In this article,
Bernstein et al. (2017) compared the immunization uptake rates of HPV, menACWY, and Tdap
and provides that the uptake of meningococcal conjugate and HPV vaccines remain lower with
HPV being the lowest of all. HPV vaccination rates are also lower among boys than girls with a
lower percentage of girls, 43 percent completing the three doses.
Bernstein et al. (2017) recommend that there is a need to understand the barriers to
immunization to help address the challenges. One of the challenges identified is that healthcare

IMMUNIZATION 5
providers do not show consistency in recommending these vaccines to patients. For instance, one
research showed that only 60% of physicians recommended HPV vaccines to 11 and 12-year-old
girls. Another barrier that is a predisposing factor is individual beliefs and lack of interest, all of
which influence delivery and acceptance of vaccines. The paper also cites the lack of parental
acceptance, where many parents find no need for the vaccine, which is contributed to a lack of
sufficient knowledge on the vaccines. For instance, Bernstein et al. (2017) provide that most
parents of adolescents decline the vaccine citing that their children are not at risk of getting the
disease, lack of trust in the vaccine, and fear of adverse effects. Lastly, misinformation on the
internet influence acceptance to immunization. Bernstein et al. (2017) recommend the need for
creating awareness and educating parents and their adolescent children on the health benefits of
these vaccines and the complications associated with diseases bring to avoid misinformation.
Burns, J. L., Walsh, L. J., & Popovich, J. M. (2010). Continuing Education: Practical Pediatric
and Adolescent Immunization Update. The Journal for Nurse Practitioners, 6(4), 254-
266. https://doi.org/10.1016/j.nurpra.2010.01.012
This article reports that nurse practitioners have a crucial role to play in the immunization
of adolescent children. For instance, Burns et al. (2010) provide that it is the role of NPs to be
aware and understand the new vaccines and immunization schedules to ensure they provide the
most up to date care to the targeted populations in the bid to meet Healthy People 2020
immunization goals. The paper also notes that vaccines played a critical role in eradicating
smallpox and poliomyelitis in the 90s. Burns et al. (2010) also discuss the predisposing factors
that hinder immunization efforts such as parental concerns and health disparities in
immunization, especially among African Americans low-income adolescents, who show low
vaccination rates than their Caucasian counterparts. For instance, the article provides that among

IMMUNIZATION 6
adolescents between 13 to 17 years, only 36 percent of African Americans were vaccinated
against Varicella and 42 percent against Tdap. Also, Burns et al. (2010) provide that Caucasian
adolescents were more informed about HPV that African American adolescents, who fail to
regard cervical cancer as a threat to themselves. Other issues that are reported to result in low
vaccine uptake in the article include a lack of mandatory visits for adolescent preventive care
Enabling factors that lack include the presence of a nationwide immunization tracking
system, which means parents do not have access to vaccine information systems regarding the
vaccines that their children have received. Burns et al. (2010) provide that the enabling factors
that promote behavior, belief, and attitude change can be reinforced by giving adolescent support
in their health. Parental and teenage education on vaccines can help address the predisposing
factors associated with lack of knowledge and ensure that their children do not miss vaccines.
This article shows that there is a need for improving immunization intervention programs for
adolescents. School-based health care centers are suggested as an effective solution to these
problems.
Federico, S. G., Abrams, L., Everhart, R. M., Melinkovich, P., & Hambidge, S. J. (2010).
Addressing adolescent immunization disparities: a retrospective analysis of school-based
health center immunization delivery. American journal of public health, 100(9), 1630–
1634. https://doi.org/10.2105/AJPH.2009.176628
The authors in this paper carried out a retrospective analysis to determine the
effectiveness of immunization delivery in community health centers(CHCs) compared to that of
school-based health centers (SBHC). According to Federico et al. (2010), SBHCs are primary
care clinics within the school premises and are considered critical in delivering immunization
among adolescents. Federico et al. (2010) argue that the current healthcare delivery system is

IMMUNIZATION 7
insufficient in providing immunization services to adolescent children, especially in multi-dose
vaccination series.
The study finding in the article provides that SBHCs were more effective in improving
adolescent uptake of vaccination. Also, adolescents in SBHCs were more likely to complete their
vaccine series dose, despite their financial and insurance status. In this case, Federico et al.
(2010) provide that SBHCs were more superior to CHCs in ensuring completion of the vaccine
doses. The research findings show that SBHCs can overcome utilization barriers in different
ways that are not documented. This includes serving people with significant health disparities,
including those who do not speak English, people without public insurance coverage, since these
characteristics are associated with reduced access to care. Another reason why Federico et al.
(2010) recommends the utilization of SBHCs is that these facilities help overcome traditional
barriers that hinder access to health care since they are located in schools that serve ethnically
and racially diverse students, as well as low-income adolescents. These facilities also have the
resources and infrastructure needed for sufficient and efficient provision of comprehensive
primary care.
Other than the effective delivery of vaccines to underserved and racial/ethnic minorities,
SBHCs can easily see patients for multiple visits than community health centers. They also have
a reminder recall system, a recognized method of improving vaccine dose series completion.
Also, Federico et al. (2010) provide that SBHCs serve populations less prone to migration,
making it easier to implement a tracking system. Other advantages that act as enablers and
reinforce are school-based health centers' ability to reduce cost barriers, in terms of out-of-pocket
expenses, transportation cost, and the troubles of adolescents going away from class/school for
vaccination.

IMMUNIZATION 8
Greenfield, L. S., Page, L. C., Kay, M., Li-Vollmer, M., Breuner, C.C., & Duchin, J.S. (2015).
Original article: Strategies for Increasing Adolescent Immunizations in Diverse Ethnic
Communities. Journal of Adolescent Health, 56, S547-S53.
https://doi.org/10.1016/j.jadohealth.2014.10.274
This paper's authors purposed to determine the adolescent knowledge and attitudes
towards various vaccines such as Tdap, MCV4, and HPV, among Somali, Ethiopian, Somali and
other communities in Washington. A report of Greenfield et al. (2015) findings shows that
predisposing factors such as reduced knowledge and awareness among adolescents and their
parents resulted in low immunization coverage in these communities. For instance, the report
provides that most of the parents from these communities had not heard of the meningococcal
conjugate, Tdap, and HPV vaccines. At the same time, only a few adolescents knew about them.
The knowledge gap has been identified in different studies to be a common factor hindering
acceptance to vaccination.
Besides the limited knowledge about the recommended vaccines for adolescents,
Greenfield et al. (2015) report that parents and some of the adolescents held various
misconceptions and beliefs about vaccine-preventable diseases, most of which varied with the
country of origin. An example provided by the author is Eritrea, where parents believe that
meningococcal disease is caused by the scorching effects of sun and heat. In this case, this
disease was not a concern for them since they live in areas with tepid climate.
Another factor that hinders uptake of vaccines by adolescents is the lack of
recommendations by healthcare providers, who are regarded as the trusted source of health
information by parents. Other factors include failure to access health information relating to

IMMUNIZATION 9
vaccines in native languages. In this case, Greenfield et al. (2015) recommend the need for
outreach health education programs to ensure such communities thrive in their health.
Katz, I.T., Bogart, L. M., Fu, C. M., Liu, Y., Cox, J. E., Samuels, R. C., Chase, T., Schubert, P.,
& Schuster, M. A. (2016). Barriers to HPV immunization among blacks and Latinos: a
qualitative analysis of caregivers, adolescents, and providers. BMC Public
Health 16, 874. https://doi.org/10.1186/s12889-016-3529-4
In this paper, the barriers that result in low HPV immunization among Latinos and Blacks
were analyzed. Katz et al. (2016) provide that HPV infection is one of the most transmitted STIs
in the IS, with over 26,000 cancers attributed to HPV. Despite this risk and the
recommendations that eleven and twelve years old get the three-dose series of the HPV vaccine,
the immunization coverage rates are still low, compared to other vaccines. Also, Latinos and
Blacks are less likely to complete the doses. Among the challenges that hinder vaccination
among adolescents is that they are directly involved in decision-making compared to younger
children. Also, care providers and caregivers play a critical role. For instance, Katz et al. (2016)
argue that research shows that improving vaccine uptake requires provider recommendation and
effective communication with caregivers.
This article's research findings show that individual and system-level factors act as
barriers to immunization uptake among adolescents. For instance, mistrust is a common factor
among caregivers and adolescents who argue that the vaccine is new and less trustworthy than
other vaccines that have existed over time. In this case, the view is that the vaccine is potentially
untested. Katz et al. (2016) argue that families feel that they lack sufficient information to make
informed decisions and thus need health education regarding the need and importance of the
HPV vaccine. On the other hand, system-level barriers are attributed to healthcare provider

IMMUNIZATION 10
perceptions. They feel that the dosage schedule does not match other standard clinical visits,
which contributes to failure in completing the series. Also, there lacks a standardized reminder
and delivery process, and healthcare providers feel that the administration of multiple vaccines in
the same clinic visit is overwhelming for adolescents. In this case, Katz et al. (2016) give an
overview of vaccine uptake barriers that can help design appropriate interventions to address
these barriers.
Salazar, K., Seib, K., Underwood, N., Gargano, L., Sales, J., Diclemente, R., Murray, D.,
Morfaw, C., & Hughes, J. (2016). Recommendations for Structure and Content for a
School-Based Adolescent Immunization Curriculum. Health Promotion Practice, 17(4),
512-520. htttps://doi.org/10.1177/1524839915627458
In this article, Salazar et al. (2016) purposed to develop recommendations for a school-
based immunization curriculum and schedule for adolescents. In the report, the rate of adolescent
immunization coverage lags behind even though there is high utilization of childhood
vaccinations. Salazar et al. (2016) report that the recommended vaccines for adolescents
between 11 and 18 years include HPV; meningococcal conjugate; pertussis, diphtheria, and
tetanus vaccines; and the influenza vaccine. The authors also provide that the current coverage in
Georgia is below the Healthy People 2020 goal of 80%. This calls for action for the development
of an intervention to increase immunization coverage.
The article provides that school communities can play a critical role in educating
adolescents about health-related issues, including preventative measures such as vaccine
utilization. In this case, Salazar et al. (2016) argue that adolescent knowledge and awareness of
immunization is crucial within the school system since this can help ensure communities are
protected from a potential disease outbreak and spread. The authors developed a plan for school

IMMUNIZATION 11
intervention in adolescent immunization by including the schedule in the school curriculum. This
intervention was informed by the fact that students spend a significant amount of time at school,
which makes the institution an excellent target location of vaccination interventions.
Salazar et al. (2016) report that teachers' recommendations in focus group discussions
could enhance student knowledge and awareness on adolescent immunization and help change
pre-existing negative beliefs, attitudes, and improve acceptance of vaccination among the
teenage population.
Salmon, D.A., Dudley, M.Z., Glanz, J.M., & Omer, S.B. (2015). Vaccine Hesitancy Causes,
Consequences, and a Call to Action. American Journal of Preventive Medicine and
Elsevier Ltd, 49(6S4): S391–S398.
In this article, Salmon et al. (2015) provide an overview of the factors that result in
vaccine hesitancy, the impacts, and call to action to address the problem. According to Salmon et
al. (2015), vaccine hesitancy is the decline or delays that precede acceptance to vaccines
resulting in failure to complete doses or ensure consistency. Findings in the article show that
there exists a wide range of factors that contribute to vaccine hesitancy. This includes factors
such as adverse effects, the mandatory nature of vaccines, lack of trust in public health agencies,
and lack of knowledge or unfamiliarity with the diseases being vaccinated against.
In the article, Salmon et al. (2015) argue that the refusal, delay, and acceptance of
vaccines can be measured by identifying people's beliefs and attitudes (predisposing factors). For
instance, the author provides that parents who are hesitant to accept their adolescent children's
vaccination are usually vulnerable to misinformation factors. According to Salmon et al. (2015),
vaccine hesitance is an issue of concern that needs to be addressed considering that the vaccine's

IMMUNIZATION 12
effectiveness in preventing the vaccine-preventable disease relies on timely vaccination. In this
case, the issues of hesitancy need to be addressed at individual, health system, provider, and
national levels by understanding the trust issues, promoting transparency, and ensuring effective
communication to doctors, parents, and adolescents with vaccine concerns. Also, Salmon et al.
(2015) provide that even though vaccines have a high potential to prevent illnesses and save
lives, this potential depends on parents' acceptance of the vaccines. This means having
confidence and trust in the vaccines, the presence of healthcare providers who recommend them
and designing systems that ensure vaccines are safe.

