


1
Gretel
DJ Guidance
APA, diseases, disorders, theories are lower case unless then are proper nouns.
Cast a "wide" net of problem areas for the client in step 1
For step 2, make sure to offer which one of the 4 themes you are organizing the clinical data from step 1.
Step 3 is a grouping by theory. I would avoid any treatment language or explanation of the theory. It is short and to the
point based natural theory groupings.
In step 4, make sure to offer the deeper issue based on your theory as well.
Make sure to avoid any treatment info in CP-CC. This part of the golden thread is to "understand" the problem via a
theory.
The cc narrative is the use of theory to understand. So use cc narrative as a place to explain step 3 and 4 and
connection to client problems.
Authors Write up
Introducing the Character
Gretel is the young protagonist in the Brothers Grimm fairy tale Hansel and Gretel, which first appeared in
print centuries ago and has since been depicted in a variety of media, including: short films, television cartoons,
and an 1893 opera of the same name by 19th-century playwright Engelbert Humperdinck. Hansel and Gretel is
a beloved fairy tale about a woodcutter’s children who suffer the loss of their mother and who must then endure
an evil stepmother (despite the common occurrence of blended families in contemporary life, stepparents often
are stereotyped as “evil” in traditional fairy tales). As often happens in such old-school fairy tales, the
woodcutter, about whom we know little other than that he is a hard worker, falls prey to his new wife’s desires
to be rid of Hansel and Gretel. She convinces him to cast them into the woods where they find a magical
gingerbread house inhabited by a witch. Although the witch welcomes the children, they soon discover that she
plans to eat them. Upon discovering her nefarious plan, Hansel pushes the witch into the oven. Thinking that
the witch is dead, the children remain in the cottage and eat candy and sweets for days before finding their way
home thanks to a marked path that they had cleverly left behind. The father, who was heartbroken over the loss
of his children, eagerly welcomes them back and rids the family, once and for all, of his evil-doing wife. Hansel
and Gretel is a timeless tale about parental loss, betrayal, and the resourcefulness and resiliency of children.
Using Hansel and Gretel as our starting point, the following basic case summary and diagnostic impressions

2
explore a clinically significant pattern of hostile and defiant behaviors we believe a similar 10-year-old girl
named Gretel might be experiencing.
Basic Case Summary
Identifying Information. Gretel Gerstenhagen is a 10-year-old Austrian girl who is a fourth-grade student at the
Gingerbread Learning Academy. Currently she lives at home with her fraternal twin, Hansel, her father, and
her

3
stepmother, who only recently became a member of the family. In appearance, Gretel can be characterized as
“a rosy-cheeked, blue-eyed girl with curly blond hair.” She was dressed in a traditional Germanic child’s outfit,
left over from a school play in which she starred, which she reported wearing “because it annoys my
stepmother.” She lives in a socioeconomically lower middle-class neighborhood, her father is a skilled
carpenter, and her stepmother works in the home.
Presenting Concern. Gretel was sent to the school counselor’s office for an initial meeting by the assistant
principal because she has several times stolen another student’s lunchbox “as a joke” and refused her teacher’s
request to return the hidden lunchbox at lunchtime. Gretel had been sent to the principal’s office on several
occasions for similar behavior, which seemed to have escalated soon after her father remarried to a woman the
child referred to as a “witch.” Gretel also has been diagnosed with juvenile diabetes.
Background, Family Information, and Relevant History. Gretel and her fraternal twin Hansel were born in
Vienna, Austria, to a fourth-generation military family headed by a father who worked as a skilled carpenter
and traveled frequently, following house-building demand across the region, and a mother who was bedridden
throughout her pregnancy and sick for the first 2 years of the children’s lives. Reports indicate that Gretel and
her brother were only allowed to visit their mother at her bedside for short periods. A day before their third
birthday, their mother died, and soon after the father brought an au pair into the house. Apparently,
unbeknownst to the father, the au pair was bringing men into the family home when the father was away. Gretel
and her brother learned early how to manipulate this woman, whom they referred to as the “evil witch” and
who reciprocated in kind with harsh punishment and withdrawal of privileges. Gretel recalled how the au pair
used to bake gingerbread houses and eat them herself while the children watched and begged. One day during a
rare outing to the park, one of the neighbors noticed the harsh manner in which the au pair treated the children
and reported directly to their father, who immediately fired her.
Following this experience, he decided to spend more time with the children in order to make up for his
many absences. By that time, the children were 7 years of age, and he decided that it would be beneficial to
move to the United States where he took a job with a contractor firm. Although Gretel was upset at leaving the

4
familiarity of Austria and the friends that she had made, she soon found a safe and secure haven at the
Gingerbread Learning Academy, where she and Hansel were enrolled in the third grade. Soon after the
relocation, Hansel and Gretel’s father married for a second time to a woman who had never wanted children but
who fell in love with their father.
Several months after marrying, Gretel and Hansel’s father returned to his busy work life, leaving the
children primarily in the care of their new stepmother, who like the au pair they had in Austria, put her needs
before those of the children. She would spend long hours on the phone talking to friends, neglecting the
children, leaving them to fend for themselves, do their own homework, and even make their own food. Gretel
became very adept at sneaking candy from the cupboards as well as stealing it from the small grocery at the
corner of their street. Gretel also developed what teachers and her father described as a “short fuse,” becoming
touchy in response to even very minor adult feedback about her behavior, loudly angry at perceived insults,
and argumentative at home, in class, and in the Gingerbread Afterschool Program. When household chores
such as cleaning the playroom were left undone, she wrongly blamed her brother; at school, she blamed
classmates for incidents on the playground. Increasingly, she yelled at her stepmother at home, muttered under
her breath at her classroom teacher, and made a clear point of being out of her seat during classroom quiet
time.
Characteristically, after a particularly unpleasant evening with the stepmother, Gretel and Hansel ran away from
home, living in a small park by the home, and subsisting only on the candy and cookies that they had pirated
away before their departure, which Gretel said she did “to show that witch!” It was at that point that Gretel and
Hansel’s father were summoned to the school and told that unless he took immediate action to control his
daughter (and son), they would be removed from the school and possibly even the home. Upon hearing this and
realizing that their plan had failed, Gretel told her teacher “maybe I’ll just kill myself . . . that’ll teach her.”
Goals for Counseling and Course of Therapy to Date. Several days after the meeting with the children, Mr.
Gerstenhagen and his wife visited with the school counselor and the district school psychologist in order to
develop a plan of action. It was decided that Gretel and Hansel would undergo psychological evaluations and

5
review by a planning team, after which a decision would be made determining whether individual or
family counseling or both would be implemented.
Diagnostic Impressions
F91.3 Oppositional Defiant Disorder
250.00 Type II Juvenile Diabetes
Z91.49 Other Personal History of Psychological Trauma
Z60.3 Acculturation Difficulty
Discussion of Diagnostic Impressions
Gretel was mandated to visit the school counselor’s office after repeatedly hiding another student’s
lunchbox as a deliberately annoying joke and refusing her teacher’s demands to return the lunchbox. Likewise,
she has engaged in purposefully annoying behavior at home (such as dressing in odd costumes). Her parents
and
teachers report that she has a “short-fused” temper, is often argumentative, easily feels resentment, and at times
seems spiteful. She also blames other children (e.g., her brother) or adults (e.g., her stepmother) for her own
misbehavior.
Gretel’s acting out behaviors are symptomatic of the disorders in the Disruptive, Impulse-Control, and
Conduct Disorders chapter of the DSM-5. This group of disorders includes: Oppositional Defiant Disorder,
Intermittent Explosive Disorder, Conduct Disorder, Antisocial Personality Disorder, Pyromania, and
Kleptomania. The common feature of this grouping is an individual’s difficulty in controlling their emotions
and behaviors in a socially acceptable manner.
Using Hansel and Gretel as our starting point in this case example, we presented a 10-year-old girl
named Gretel who was experiencing a clinically significant pattern of hostile and defiant behaviors beyond
what is normally expected among her age and cultural peer group. Her behaviors have been persistent for many
months, and they have become sufficiently problematic to impair Gretel’s family relationships at home, her

6
relationships with teachers and peers at school, and her ability to perform and succeed in the classroom. Gretel’s
behaviors suggest a diagnosis of Oppositional Defiant Disorder, the key feature of which is a pattern of
“angry/irritable mood, argumentative/defiant behavior, or vindictiveness” lasting for at least 6 months, typically
in a child under 18 years old.
One differential diagnosis might be Conduct Disorder, Childhood-Onset Type. This is another diagnosis
found among the group of Disruptive, Impulse-Control, and Conduct Disorder chapter in the DSM-5. This
diagnosis is ruled out, however, since Gretel’s behaviors, although negative and defiant, do not feature the
aggressiveness to people and animals, destructiveness, deceitfulness, and serious rule violations characteristic of
a Conduct Disorder. Another consideration is to assign no primary mental health diagnosis because oppositional
behavior is typical of certain developmental stages such as early childhood and adolescence. In turn, the
Oppositional Defiant Disorder diagnosis is appropriate only if “the frequency and intensity of the behaviors are
outside a range that is normative for the individual’s developmental level, gender, and culture” (APA, 2013, p.
462). Gretel’s behaviors meet this standard.
To round out the diagnosis, Gretel’s diabetes is listed because its presence may have impacted
significantly upon the family system. Further, her family and social stressors are emphasized in the “Other
factors” section. The information presented is consistent with the diagnosis portrayed by Gretel in this scenario.
Case Conceptualization
When Gretel came into the Gingerbread Learning Academy’s school counseling office, her counselor first
conducted an intake meeting in order to collect as much information as he could about the symptoms and
situations leading to Gretel’s referral. Included in the intake materials were a developmental history, client
report, counselor observations, child-oriented clinical interview, play observation, parent report inventories, and
information shared by Gretel’s school principal and teachers (Knell, 1993, 1994). Based on the intake, Gretel’s
counselor developed diagnostic impressions, describing her presenting concerns by Oppositional Defiant
Disorder. A case conceptualization next was developed. Whereas the purpose of diagnostic impressions is to
describe the client’s concerns, the goal of case conceptualization is to better understand and clinically explain

7
the person’s experiences (Neukrug & Schwitzer, 2006). It helps the counselor understand the etiology leading
to Gretel’s Oppositional Defiant behaviors and the factors maintaining these concerns. In turn, case
conceptualization sets the stage for treatment planning. Treatment planning then provides a road map that plots
out how the counselor and client expect to move from presenting concerns to positive outcomes (Seligman,
1993, p. 157)—helping Gretel manage her oppositional behaviors and defiant thoughts and attitudes and
improving her interpersonal interactions.
When forming a case conceptualization, the clinician applies a purist counseling theory, an integration
of two or more theories, an eclectic mix of theories, or a solution-focused combination of techniques to his or
her understanding of the client. In this case, Gretel’s counselor based his conceptualization on
psychotherapeutic integration of two theories (Corey, 2009). Psychotherapists very commonly integrate more
than one theoretical approach in order to form a conceptualization and treatment plan that will be as efficient
and effective as possible for meeting the client’s needs (Dattilo & Norcross, 2006; Norcross & Beutler, 2008).
In other words, counselors using the psychotherapeutic integration method attempt to flexibly tailor their
clinical efforts to “the unique needs and contexts of the individual client” (Norcross & Beutler, 2008, p. 485).
Like other counselors using integration, Gretel’s school counselor chose this method because he had not found
one individual theory that was comprehensive enough, by itself, to address all of the “complexities,” “range of
client types,” and “specific problems” seen among his everyday student caseload (Corey, 2009, p. 450).
Specifically, Gretel’s counselor selected an integration of (a) Child-Centered Play Therapy and (b)
Cognitive Behavioral Play Therapy. He selected this approach based on Gretel’s presentation of problematic
behaviors and his knowledge of current outcome research and recommended practice literature with clients
experiencing these types of concerns (Kazdin & Weisz, 2003; Lawrence, Condon, Jacobi, & Nicholson, 2006;
Mowder, Rubinson, & Yasik, 2009). According to the research, Cognitive Behavioral Play Therapy is one
treatment approach indicated when assisting clients who might benefit from a combination of cognitive and
behavior change, whereas an integrated approach emphasizing Child-Centered Play Therapy is indicated
when the counselor expects to facilitate the child’s own problem-solving capacity (Knell, 1993, 1994;

9
1991). The Gingerbread Child Guidance Clinic counselor is comfortable theoretically integrating these
approaches.
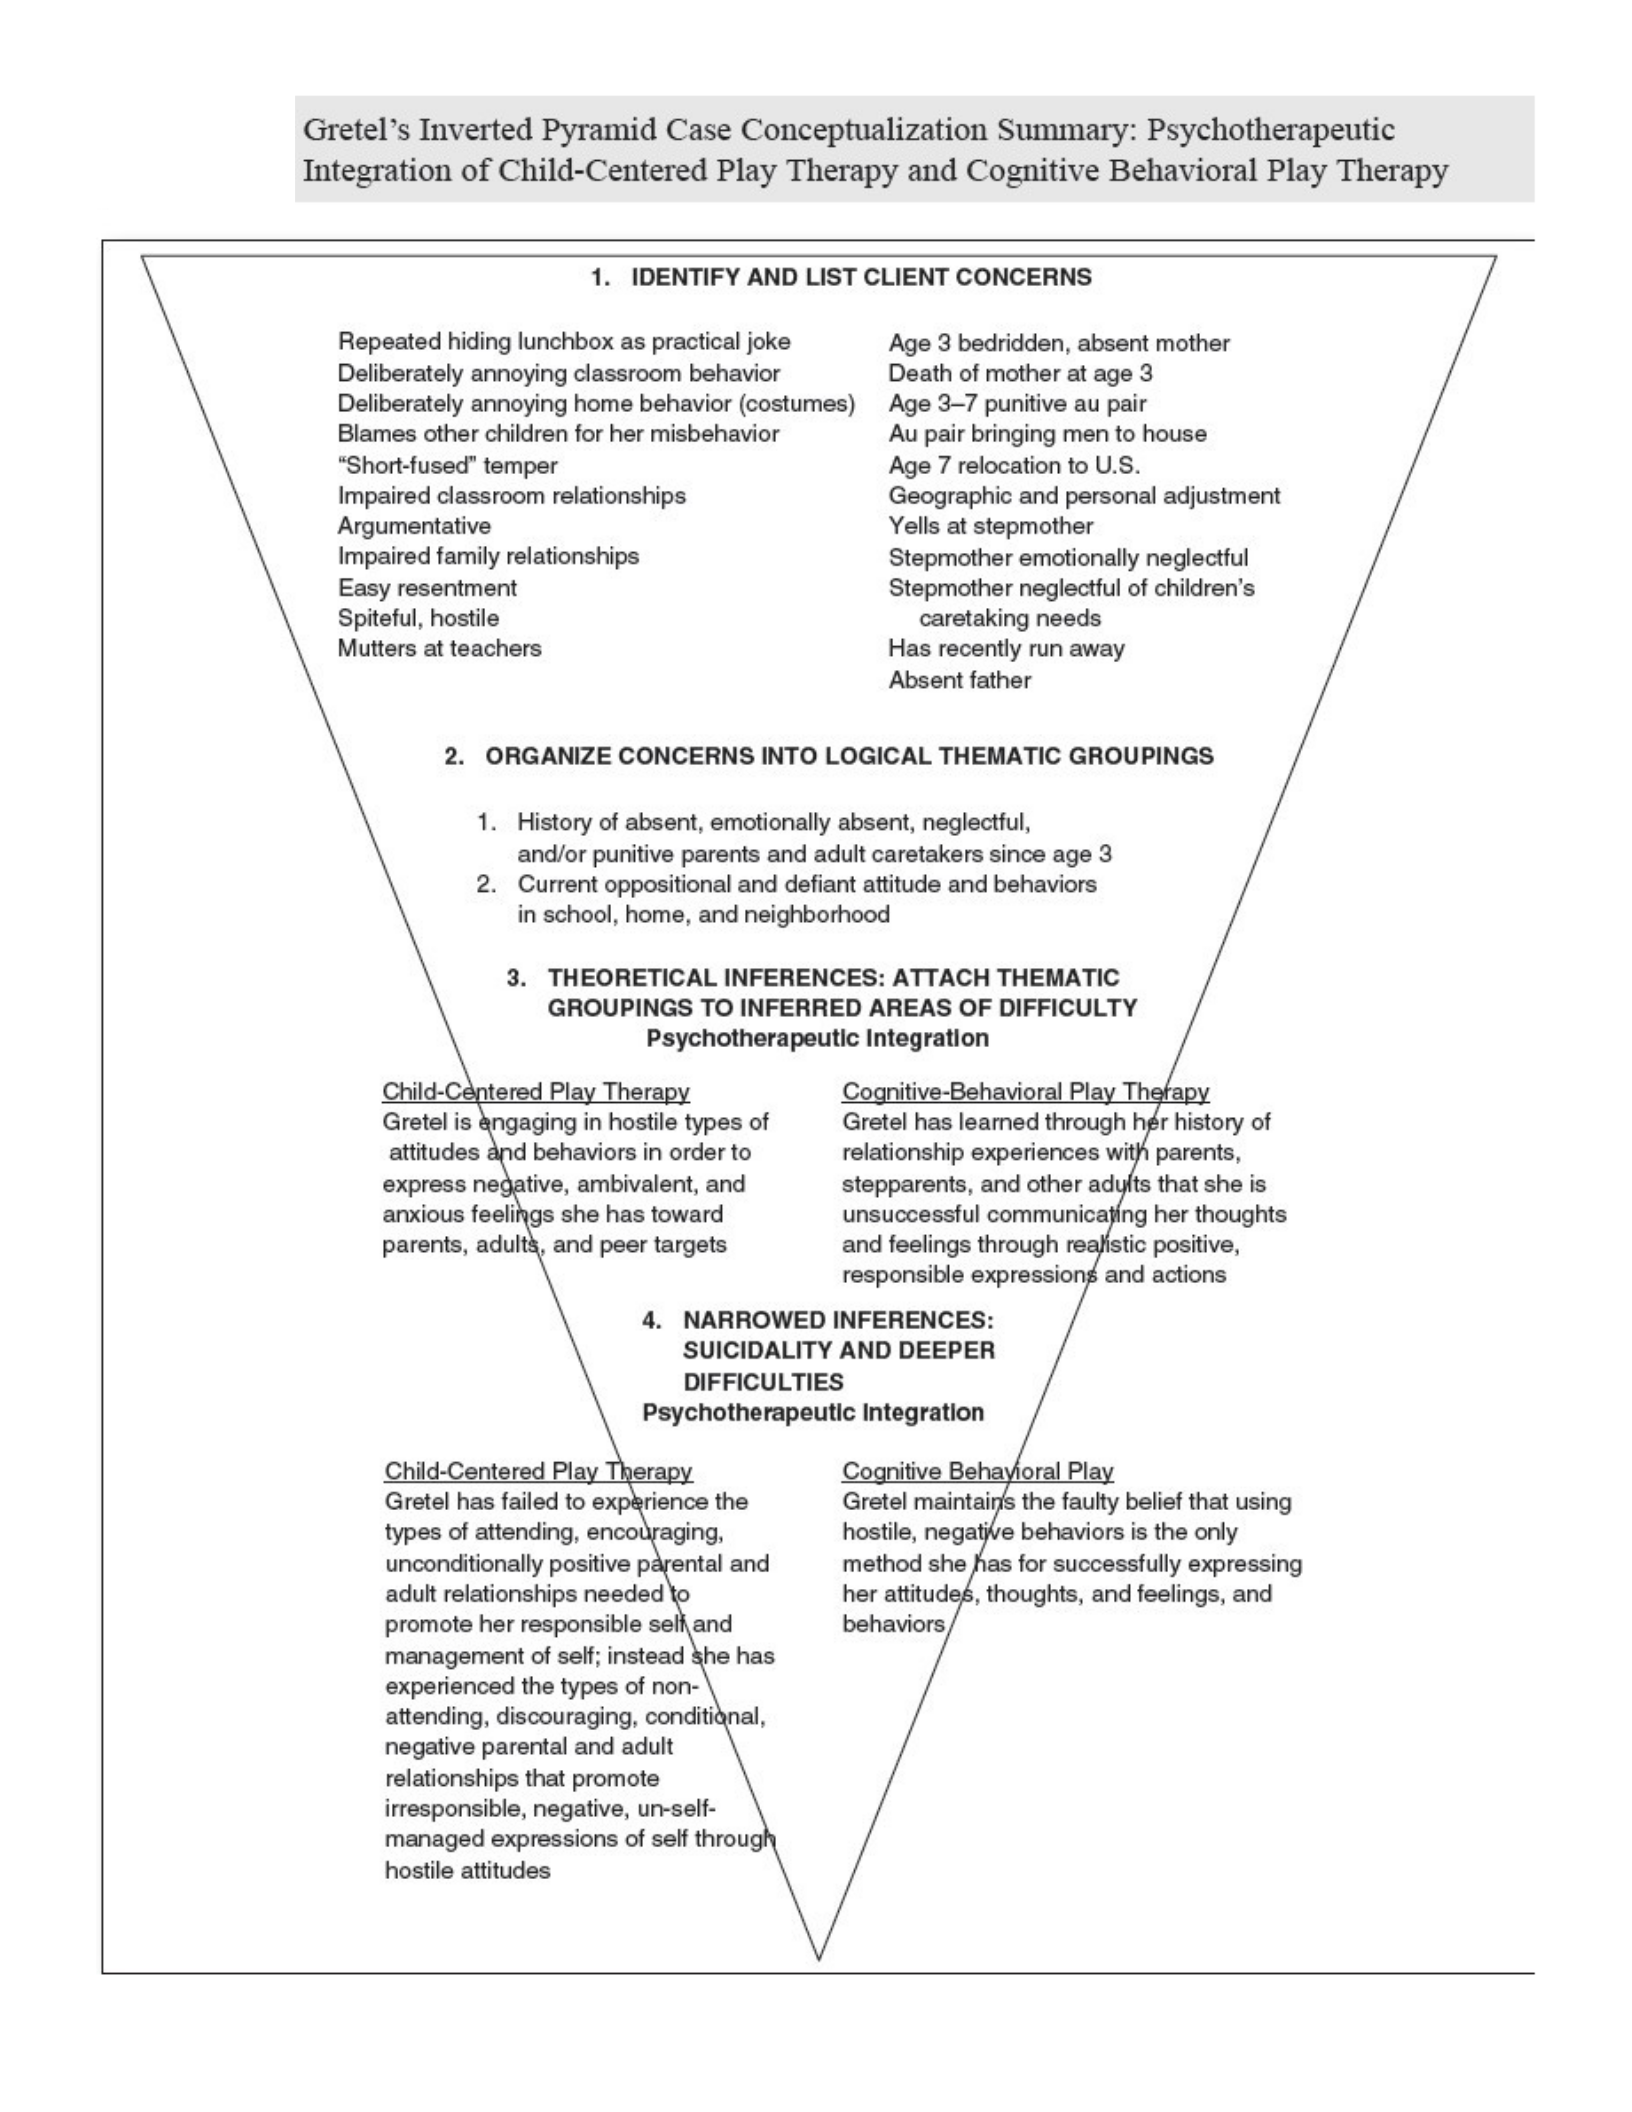
The counselor used the Inverted Pyramid Method of case conceptualization because this method is
especially designed to help clinicians more easily form their conceptual pictures of their clients’ needs
(Neukrug & Schwitzer, 2006; Schwitzer, 1996, 1997). The method has four steps: Problem Identification,
Thematic Groupings, Theoretical Inferences, and Narrowed Inferences. The counselor’s clinical thinking can be
seen in the figure that follows.
Gretel’s
Inverted
Pyramid
Case
Conceptualization
Summary:
Psychotherapeutic
Integration
of
Child-Centered
Play
Therapy
and
Cognitive
Behavioral
Play
Therapy
1.
IDENTIFY
AND
LIST
CLIENT
CONCERNS
Repeated
hiding
lunchbox
as
practical
joke
Age
3
bedridden,
absent
mother
Deliberately
annoying
classroom
behavior
Death
of
mother
at
age
3
Deliberately
annoying
home
behavior
(costumes)
Age
3—7
punitive
au
pair
Blames
other
children
for
her
misbehavior
Au
pair
bringing
men
to
house
“Short-fused"
temper
Age
7
relocation
to
U.S.
Impaired
classroom
relationships
Geographic
and
personal
adjustment
Argumentative
Yells
at
stepmother
Impaired
family
relationships
Stepmother
emotionally
neglectful
Easy
resentment
stepmother
neglectful
of
children’s
Spitetul,
hostile
caretaking
needs
Mutters
at
teachers
Has
recently
run
away
Absent
father
2.
ORGANIZE
CONCERNS
INTO
LOGICAL
THEMATIC
GROUPINGS
1.
History
of
absent,
emotionally
absent,
neglecttul,
and/or
punitive
parents
and
adult
caretakers
since
age
3
2.
Current
oppositional
and
defiant
attitude
and
behaviors
in
school,
home,
and
neighborhood
3.
THEORETICAL
INFERENCES:
ATTACH
THEMATIC
GROUPINGS
TO
INFERRED
AREAS
OF
DIFFICULTY
Psychotherapeutic
Integration
Child-Géantered
Play
Therapy
Cognitive-Behavioral
Play
Thetapy
Gretel
is
@ngaging
in
hostile
types
of
Gretel
has
learned
through
hér
history
of
attitudes
and
behaviors
in
order
to
relationship
experiences
with
parents,
express
negative,
ambivalent,
and
stepparents,
and
other
adults
that
she
is
anxious
feelings
she
has
toward
unsuccessful
communicating
her
thoughts
parents,
adult,
and
peer
targets
and
feelings
through
realistic
positive,
responsible
expressiong
and
actions
4.
NARROWED
INFERENCES:
SUICIDALITY
AND
DEEPER
DIFFICULTIES
Psychotherapeutic
Integration
Child-Centered
Play
Therapy
Cognitive
Behayioral
Play
Gretel
has
failed
to
experience
the
Gretel
maintains
the
faulty
belief
that
using
types
of
attending,
encouraging,
hostile,
negatwe
behaviors
is
the only
unconditionally
positive
parental
and
method
she
has
for
successfully
expressing
adult
relationships
needed
her
attitud
promote
her
responsible
self,
and
behaviors
management
of
self;
instead
She
has
experienced
the
types
of
non-
attending,
discouraging,
conditidnal,
negative
parental
and
adult
relationships
that
promote
irresponsible,
negative,
un-self-
managed
expressions
of self
throug
hostile
attitudes
,
thoughts,
and
feelings,
and
8

9
Step 1: Problem Identification. The first step is Problem Identification. Aspects of the presenting problem
(thoughts, feelings, behaviors, physiological features), additional areas of concern besides the presenting
concern, family and developmental history, in-session observations, clinical inquiries (medical problems,
medications, past counseling, substance use, suicidality), and psychological assessments (problem checklists,
personality inventories, mental status exam, specific clinical measures) all may contribute information at Step 1.
The counselor “casts a wide net” in order to build Step 1 as exhaustively as possible (Neukrug & Schwitzer,
2006, p. 202). As can be seen in the figure, the counselor thoroughly noted not just all of Gretel’s current
oppositional and defiant behaviors occurring at school and at home, all of Gretel’s aggressive and disrespectful
behaviors occurring with peers in various school and neighborhood settings, and her running away and
challenge of adults—but also, as much important information as he could find regarding Gretel’s earlier
developmental experiences, childhood life transitions, and parental and caretaker experiences. He attempted to
go beyond just listing the main behaviors that precipitated the referral and to be as complete as he could.
Step 2: Thematic Groupings. The second step is Thematic Groupings. The clinician organizes all of the
exhaustive client information found in Step 1 into just a few intuitive-logical clinical groups, categories, or
themes, on the basis of sensible common denominators (Neukrug & Schwitzer, 2006). Four different ways of
forming the Step 2 theme groups can be used: Descriptive-Diagnosis Approach, Clinical Targets Approach,
Areas of Dysfunction Approach, and Intrapsychic Approach. As can be seen in the figure, Gretel’s counselor
selected the Areas of Dysfunction Approach. This approach sorts together all of the Step 1 information into
“areas of dysfunction according to important life situations, life themes, or life roles and skills” (Neukrug &
Schwitzer, 2006, p. 205).
The counselor formed two groupings. He grouped together all of Gretel’s negative parental and family
experiences (loss of mother, au pair difficulties, relocation, stepmother difficulties, absent father, etc.) into the
theme “History of absent, emotionally absent, neglectful, and/or punitive parents and adult caretakers since pre-
age 3.” Likewise, he grouped together all of the remaining Step 1 items—Gretel’s many past and current hostile

10
and problematic behaviors and attitudes—into the theme “Current oppositional and defiant attitudes and
behaviors in school, home, and neighborhood.”
So far, at Steps 1 and 2, the counselor has used his clinical assessment skills and his clinical judgment to
begin critically describing Gretel’s needs. Now, at Steps 3 and 4, he applies the theoretical approach he has
selected. He begins making theoretical inferences to explain the factors leading to, and maintaining, Gretel’s
issues as they are seen in Steps 1 and 2.
Step 3: Theoretical Inferences. At Step 3, concepts from the counselor’s theoretical integration of two
approaches—Child-Centered Play Therapy and Cognitive Behavioral Play Therapy—are applied to the factors
causing, and the mechanisms maintaining, Gretel’s reasons for referral. The counselor tentatively matches the
theme groups in Step 2 with this theoretical approach. In other words, the symptom constellations in Step 2,
which were distilled from the symptoms in Step 1, now are combined using theory to show what are believed
to be the underlying processes or psychological mechanisms of Gretel’s current needs (Neukrug & Schwitzer,
2006; Schwitzer, 2006, 2007).
First, Child-Centered Play Therapy was applied primarily to Gretel’s attitudes and use of behaviors for
self-expression. According to the Child-Centered Play Therapy conceptual model, adult-child relationships
characterized by warm, genuine, unconditional positive regard set the conditions for the child to develop his or
her natural “innate human capacity” to “strive toward growth and maturity,” become “constructively self-
directing,” and be able to responsibly and realistically express his or her thoughts, feelings, and attitudes
(Landreth & Sweeney, 1997, p. 17). Without these relationship conditions, or with contradictory conditions,
the child may not develop a positive striving, constructive self-direction, and responsible and realistic self-
expression; instead, she may develop in problematic or frustrating directions (Landreth, 1991; Landreth &
Sweeney, 1997). Correspondingly, as can be seen in the figure, Gretel’s counselor made the theoretical
inference that “Gretel is engaging in hostile types of attitudes and behaviors in order to express negative,
ambivalent, and anxious feelings she has toward parents, adults, and peer targets.”

11
Second, Cognitive Behavioral Play Therapy was applied primarily to Gretel’s learned behaviors.
According to the Cognitive Behavioral Play Therapy model, cognitive and behavioral learning principles apply
to children so that the child’s behaviors often may be understood as stemming from faulty learning or faulty
beliefs; his or her thoughts, feelings, fantasies, and environment all may contribute to inaccurate learned
behaviors and reactions (Knell, 1993, 1994). As also can be seen in the figure, when Gretel’s counselor
additionally applied these concepts, he developed a further Step 3 inference, as follows: Gretel has learned
through her history of relationship experiences with parents, stepparent, and other adults that she is
unsuccessful at communicating her thoughts and feelings through realistic positive, responsible expressions and
actions.
Step 4: Narrowed Inferences. At Step 4, the clinician’s selected theory continues to be used to address still-
deeper issues when they exist (Schwitzer, 2006, 2007). At this step, “still-deeper, more encompassing, or more
central, causal themes” are formed (Neukrug & Schwitzer, 2006, p. 207). Gretel’s counselor continued to use
psychotherapeutic integration of two approaches.
First, continuing to apply Child-Centered Play Therapy concepts at Step 4, the counselor presented a
single, deepest theoretical inference that he believed to be most fundamental for Gretel from a child-centered
perspective: Gretel has failed to experience the types of attending, encouraging, unconditionally positive
parental and adult relationships needed to promote her responsible, positive, self-directed expression of self and
management of self; instead, she has experienced the types of nonattending, discouraging, conditional, negative
parental and adult relationships that promote irresponsible, negative, un-self-managed expressions of self
through hostile attitudes and behaviors. Second, continuing to apply Cognitive Behavioral Play Therapy
concepts, Gretel’s counselor presented an additional, complementary deep theoretical inference, as follows:
Gretel maintains the faulty belief that using hostile, negative behaviors is the only method she has for
successfully expressing her attitudes, thoughts, and feelings. These two narrowed inferences, together, form the
basis for understanding Gretel’s current counseling situation as we have written her imagined clinical case
illustration.

12
When all four steps are completed, the client information in Step 1 leads to logical-intuitive groupings
on the basis of common denominators in Step 2, the groupings then are explained using theory at Step 3, and
then, finally, at Step 4, further deeper explanations are made. From start to finish, the thoughts, feelings,
behaviors, and physiological features in the topmost portions are connected on down the pyramid into deepest
dynamics.

