



JEFF’S CASE 1
Jeff’s Case
Gricelda Rodriguez
School Of Behavioral Sciences, Liberty University
JEFF’S CASE 2
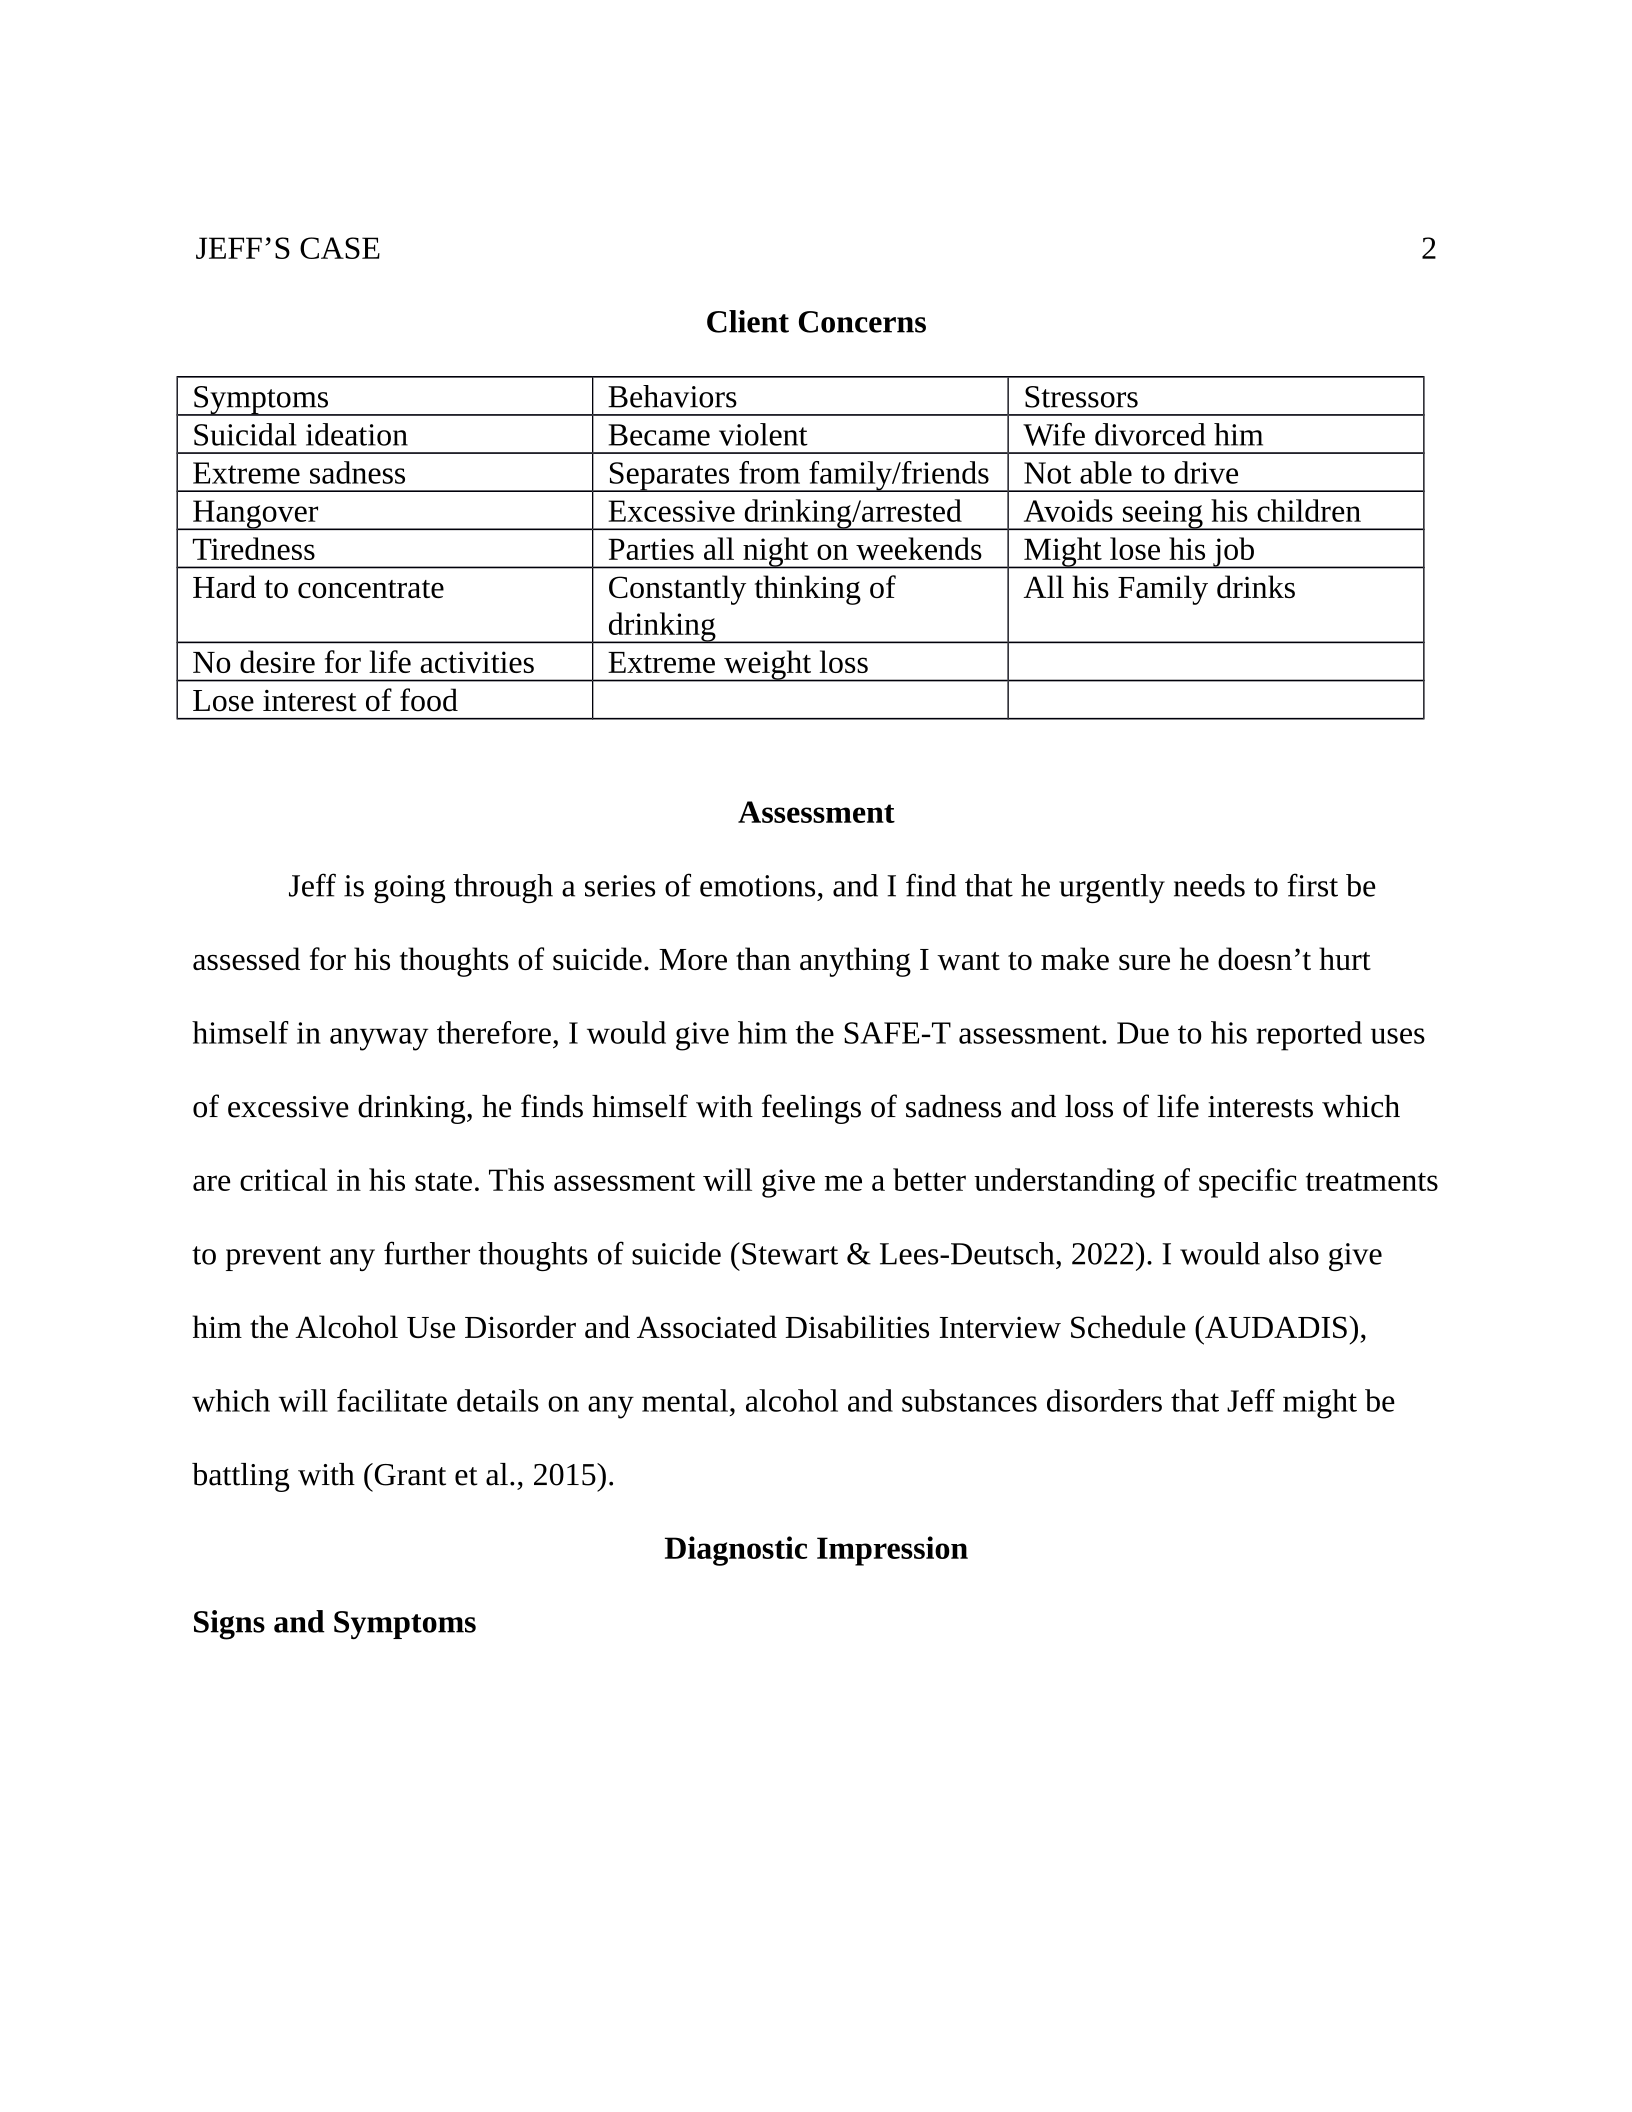
Client Concerns
Symptoms Behaviors Stressors
Suicidal ideation Became violent Wife divorced him
Extreme sadness Separates from family/friends Not able to drive
Hangover Excessive drinking/arrested Avoids seeing his children
Tiredness Parties all night on weekends Might lose his job
Hard to concentrate Constantly thinking of
drinking
All his Family drinks
No desire for life activities Extreme weight loss
Lose interest of food
Assessment
Jeff is going through a series of emotions, and I find that he urgently needs to first be
assessed for his thoughts of suicide. More than anything I want to make sure he doesn’t hurt
himself in anyway therefore, I would give him the SAFE-T assessment. Due to his reported uses
of excessive drinking, he finds himself with feelings of sadness and loss of life interests which
are critical in his state. This assessment will give me a better understanding of specific treatments
to prevent any further thoughts of suicide (Stewart & Lees-Deutsch, 2022). I would also give
him the Alcohol Use Disorder and Associated Disabilities Interview Schedule (AUDADIS),
which will facilitate details on any mental, alcohol and substances disorders that Jeff might be
battling with (Grant et al., 2015).
Diagnostic Impression
Signs and Symptoms
JEFF’S CASE 3
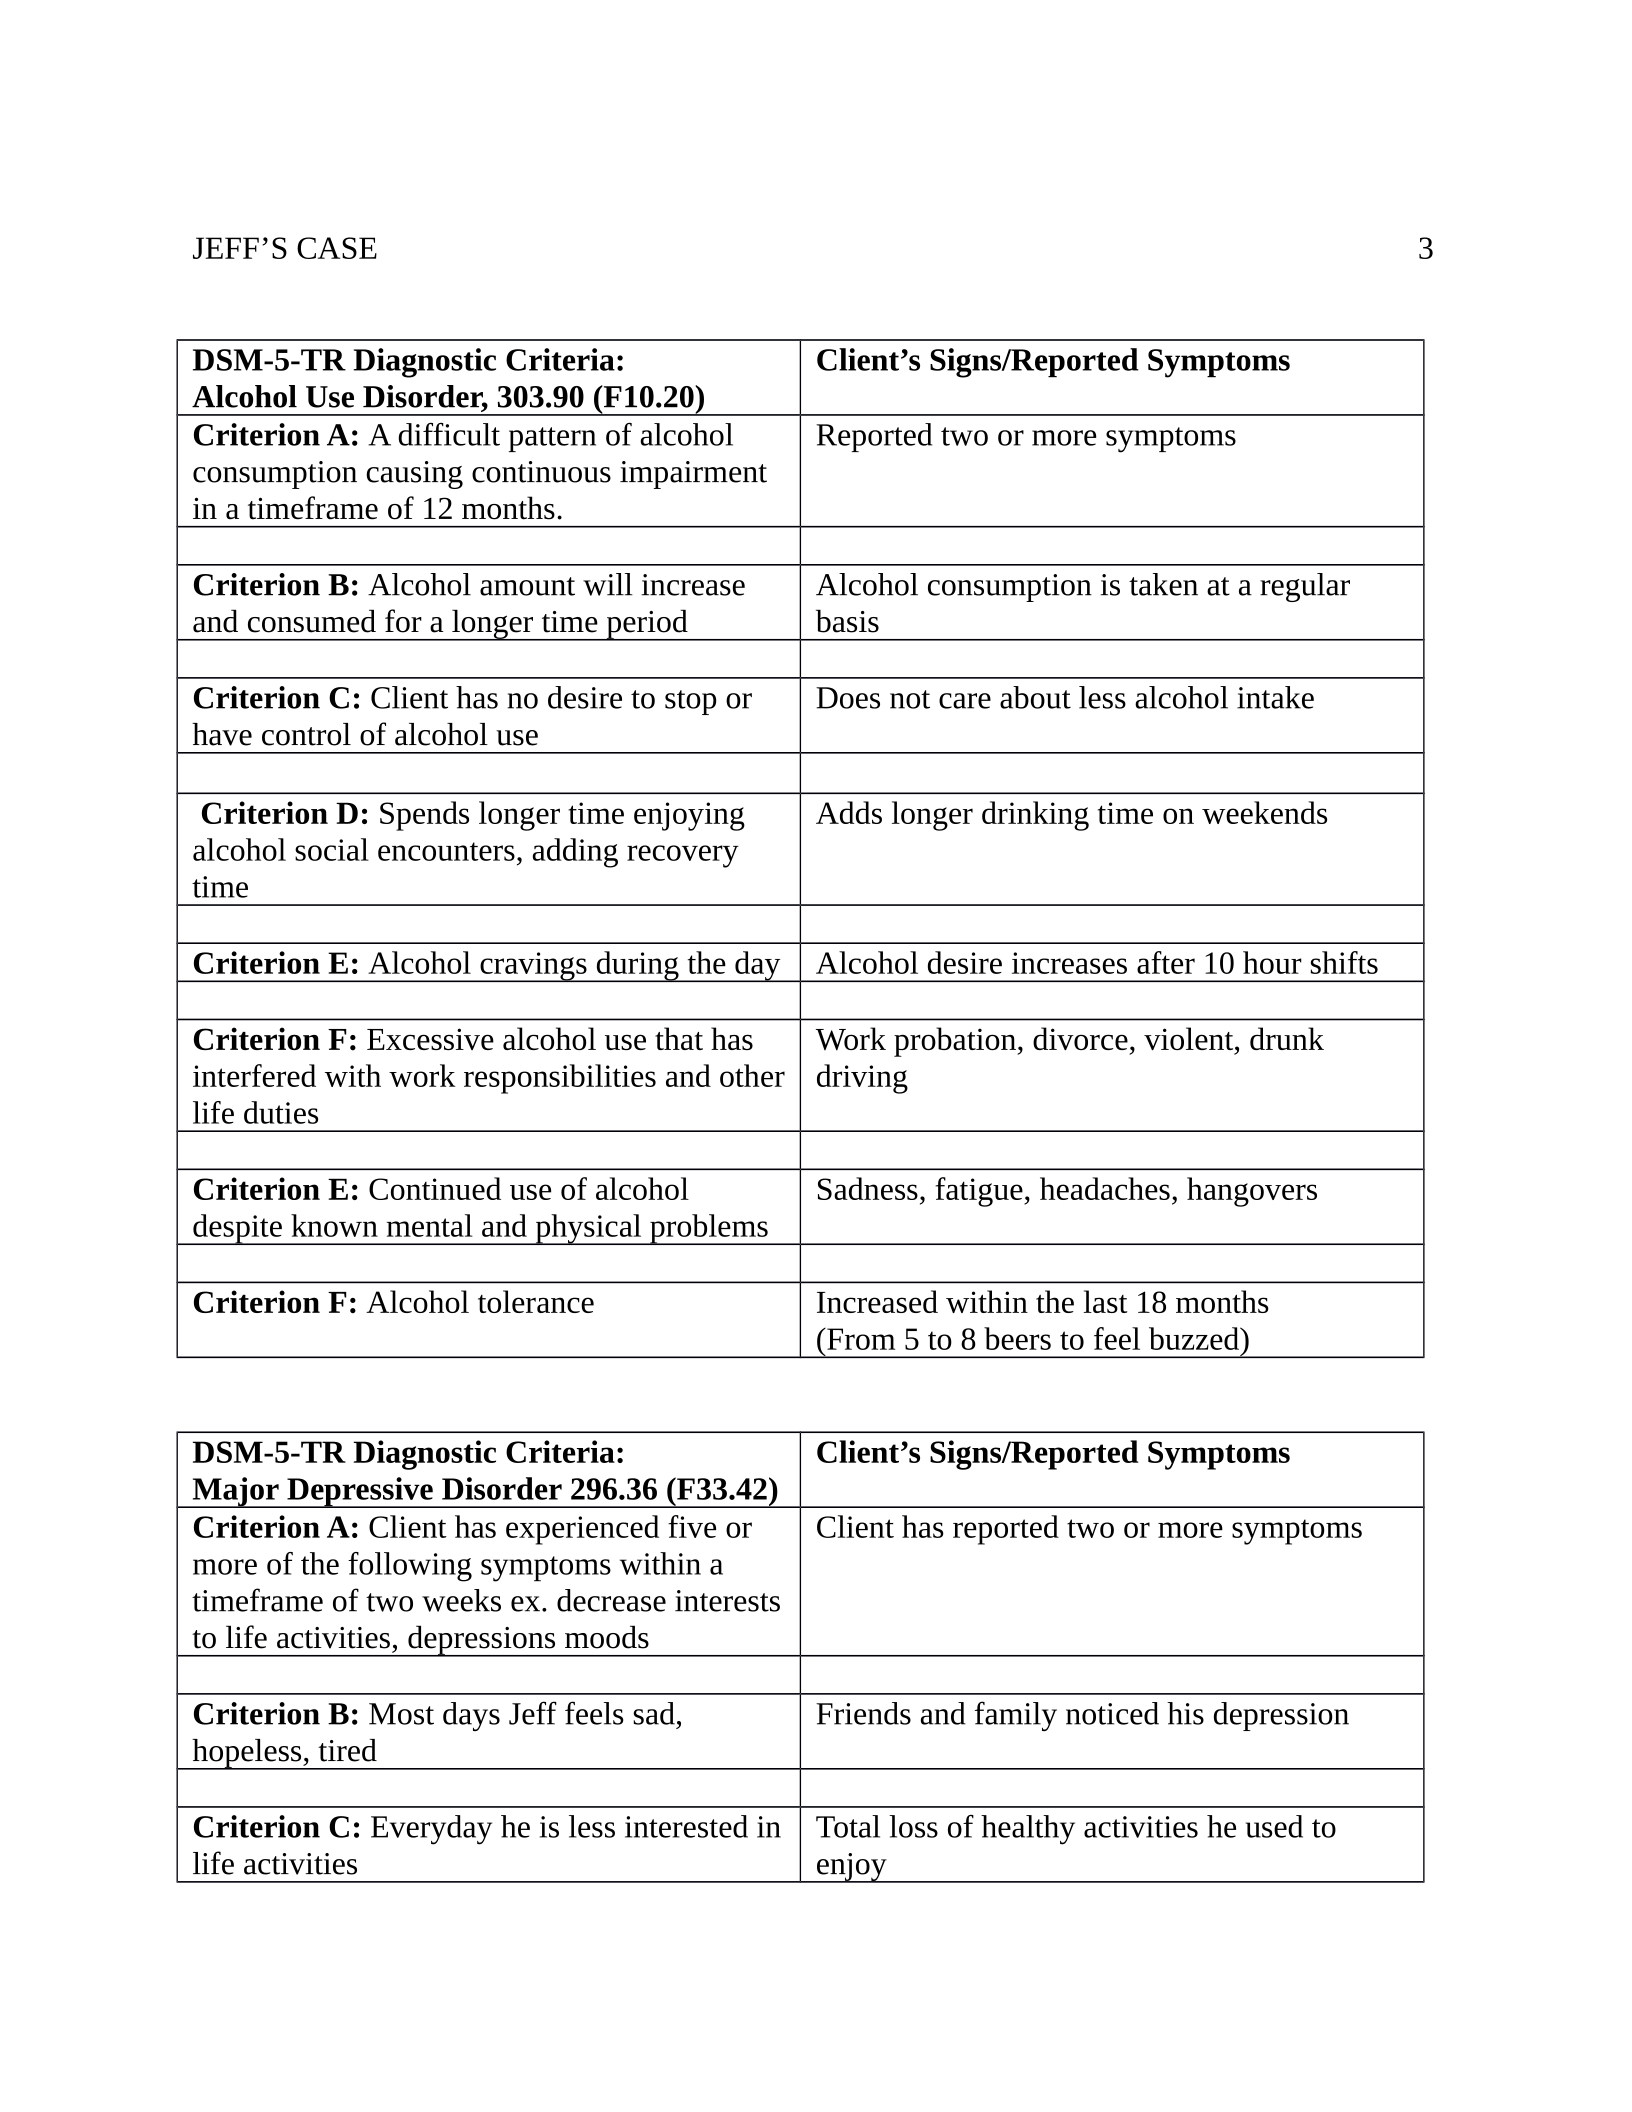
DSM-5-TR Diagnostic Criteria:
Alcohol Use Disorder, 303.90 (F10.20)
Client’s Signs/Reported Symptoms
Criterion A: A difficult pattern of alcohol
consumption causing continuous impairment
in a timeframe of 12 months.
Reported two or more symptoms
Criterion B: Alcohol amount will increase
and consumed for a longer time period
Alcohol consumption is taken at a regular
basis
Criterion C: Client has no desire to stop or
have control of alcohol use
Does not care about less alcohol intake
Criterion D: Spends longer time enjoying
alcohol social encounters, adding recovery
time
Adds longer drinking time on weekends
Criterion E: Alcohol cravings during the day Alcohol desire increases after 10 hour shifts
Criterion F: Excessive alcohol use that has
interfered with work responsibilities and other
life duties
Work probation, divorce, violent, drunk
driving
Criterion E: Continued use of alcohol
despite known mental and physical problems
Sadness, fatigue, headaches, hangovers
Criterion F: Alcohol tolerance Increased within the last 18 months
(From 5 to 8 beers to feel buzzed)
DSM-5-TR Diagnostic Criteria:
Major Depressive Disorder 296.36 (F33.42)
Client’s Signs/Reported Symptoms
Criterion A: Client has experienced five or
more of the following symptoms within a
timeframe of two weeks ex. decrease interests
to life activities, depressions moods
Client has reported two or more symptoms
Criterion B: Most days Jeff feels sad,
hopeless, tired
Friends and family noticed his depression
Criterion C: Everyday he is less interested in
life activities
Total loss of healthy activities he used to
enjoy
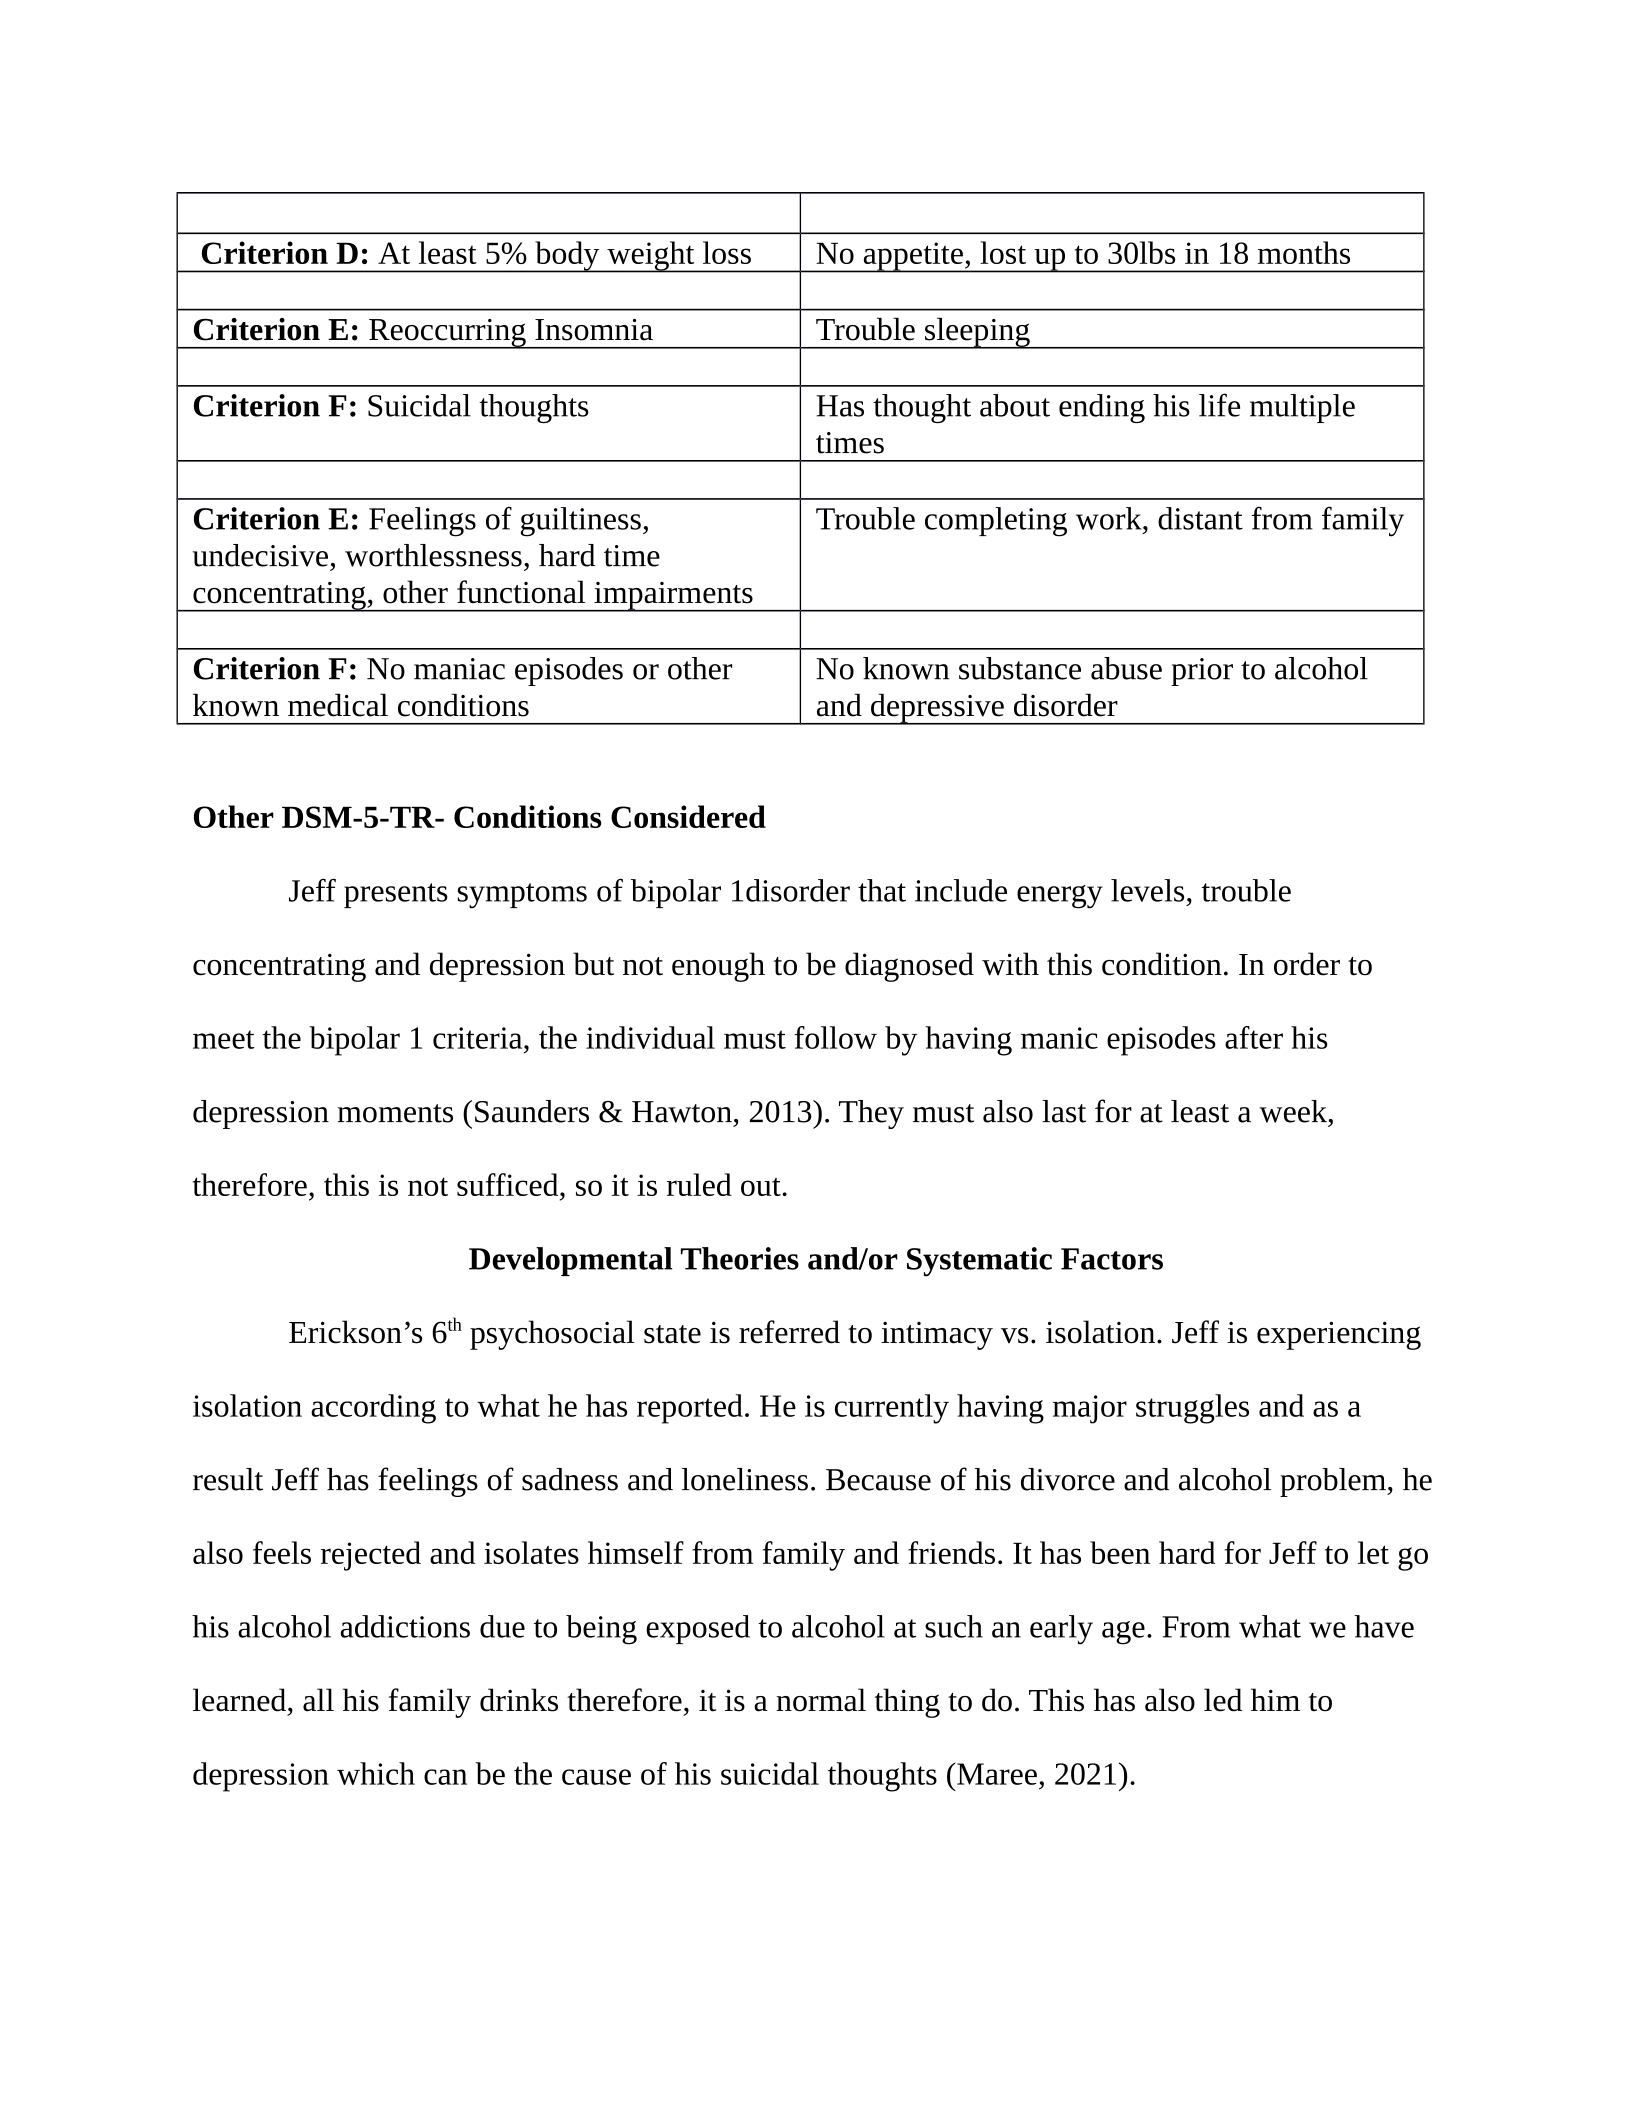
Criterion D: At least 5% body weight loss No appetite, lost up to 30lbs in 18 months
Criterion E: Reoccurring Insomnia Trouble sleeping
Criterion F: Suicidal thoughts Has thought about ending his life multiple
times
Criterion E: Feelings of guiltiness,
undecisive, worthlessness, hard time
concentrating, other functional impairments
Trouble completing work, distant from family
Criterion F: No maniac episodes or other
known medical conditions
No known substance abuse prior to alcohol
and depressive disorder
Other DSM-5-TR- Conditions Considered
Jeff presents symptoms of bipolar 1disorder that include energy levels, trouble
concentrating and depression but not enough to be diagnosed with this condition. In order to
meet the bipolar 1 criteria, the individual must follow by having manic episodes after his
depression moments (Saunders & Hawton, 2013). They must also last for at least a week,
therefore, this is not sufficed, so it is ruled out.
Developmental Theories and/or Systematic Factors
Erickson’s 6th psychosocial state is referred to intimacy vs. isolation. Jeff is experiencing
isolation according to what he has reported. He is currently having major struggles and as a
result Jeff has feelings of sadness and loneliness. Because of his divorce and alcohol problem, he
also feels rejected and isolates himself from family and friends. It has been hard for Jeff to let go
his alcohol addictions due to being exposed to alcohol at such an early age. From what we have
learned, all his family drinks therefore, it is a normal thing to do. This has also led him to
depression which can be the cause of his suicidal thoughts (Maree, 2021).

JEFF’S CASE 4
Multicultural and/Social Justice Considerations
Jeff has stated that drinking is what he has always done with his father and siblings. He
also reported that his mother is usually sad. This has led him to continue to drink throughout his
life because it is seen as a normal thing to do. He also stated that one of his siblings does not talk
to him because of the alcohol use and has lost his wife for the same reason. This has been a huge
cause of his isolation that has led him to depression. His addiction has also interfered with his job
and is close to losing that as well. Jeff has very serious issues and is in critical help due to his
thoughts of suicide. According to research, Jeff’s social factors have contributed to his drinking
behaviors developing throughout the years because he was exposed in his early childhood and
has now developed stronger drinking habits (Ratts & Pederson, 2014).
Treatment Recommendations
Key Issues for Treatment
Depression
Alcohol Use
Suicidal Thoughts
Recommendations for Individual Counseling
My biggest concern is Jeff’s suicidal thoughts; therefore, I would first recommend
Cognitive behavioral therapy (CBT). This treatment can help navigate the therapist into getting
further details and provide an intervention plan against his suicide ideation. Research tells us that
CBT has been effective in helping individuals identify negative thoughts that contribute to
alcohol abuse. The counselor can also use this time to efficiently build a connection with Jeff

without being judgmental, so he understands there is no need to be defensive about his drinking
problem (Hayes & Hofmann, 2018.) Another treatment I would recommend is motivational
enhancement therapy (MET), which has been proven to be a short but an effective treatment for
alcohol disorders. MET uses the transtheoretical model of change which helps individuals
understand their behaviors and motivates them to recover (Korte & Schmidt, 2015). I wouldn’t
want to overwhelm Jeff, so I think this would be something that might work in the beginning in
order to get him used to counseling sessions. MET is normally about four sessions but can go up
to six. During this treatment, the counselor will work on helping Jeff feel more confident and
willing to make that change. Jeff is suffering from depression, however because of his alcohol
addiction, I do not think it is safe to put him on any medication at this time. Instead of helping, a
mix of both can counteract and make it harder for the client’s treatment.
Special Consideration
Because Jeff is experiencing suicidal ideation, I would make that a priority. My goal is to
make sure the client is safe from any type of harm. After, I would then help Jeff control his
alcohol consumption so that he does not lose his job. He has expressed many times how much he
likes it. This can be used as a motivator to accomplish the issue. I would also work on goal
setting, and at the same time reminding him know that he has control of his actions, therefore,
setting realistic goals is a key. Through CBT and MET, Jeff will be educated on depression and
alcohol abuse and how they connect negatively. He reported his mother was mostly sad and
drinking with his family all the time, therefore, this will help him become aware of why he has
sadness and alcohol issues. Jeff does not seem to think he has a problem, especially because he
grew up drinking and continues to socialize with others that consume alcohol. My job is to

diagnose and treat him by recommending what he needs but at the end of the day, it will be up to
Jeff to decide what he really desires (France, 2015).
JEFF’S CASE 6
References
Grant BF, Goldstein RB, Smith SM, Jung J, Zhang H, Chou SP, Pickering RP, Ruan WJ, Huang
B, Saha TD, Aivadyan C, Greenstein E, Hasin DS. The Alcohol Use Disorder and Associated
Disabilities Interview Schedule-5 (AUDADIS-5): reliability of substance use and psychiatric
disorder modules in a general population sample. Drug Alcohol Depend. 2015 Mar 1;148:27-
33. doi: 10.1016/j.drugalcdep.2014.11.026. Epub 2014 Dec 8. PMID: 25595052; PMCID:
PMC5554948.
Hayes, S. C., & Hofmann, S. G. (Eds.). (2018). Process-based CBT: The science and core
clinical competencies of cognitive behavioral therapy. New Harbinger Publications.
Korte, K. J., & Schmidt, N. B. (2015). The use of motivation enhancement therapy to increase
utilization of a preventative intervention for anxiety sensitivity. Cognitive Therapy and
Research, 39, 520-530.
Maree, J. G. (2021). The psychosocial development theory of Erik Erikson: critical
overview. Early Child Development and Care, 191(7-8), 1107-1121
Ratts, M. J., & Pedersen, P. B. (2014). Counseling for multiculturalism and social justice:
Integration, theory, and application. John Wiley & Sons.
Saunders, K. E., & Hawton, K. (2013). Clinical assessment and crisis intervention for the
suicidal bipolar disorder patient. Bipolar disorders, 15(5), 575-583.
Stewart, I., & Lees-Deutsch, L. (2022). Risk assessment of self-injurious behavior and suicide
presentation in the emergency department: an integrative review. Journal of emergency


