


AMARA CASE STUDY ASSIGNMENT 1
AMARA CASE STUDY ASSIGNMENT
Ashley Hogans
School of Behavioral Science, Liberty University

AMARA CASE STUDY ASSIGNMENT 2
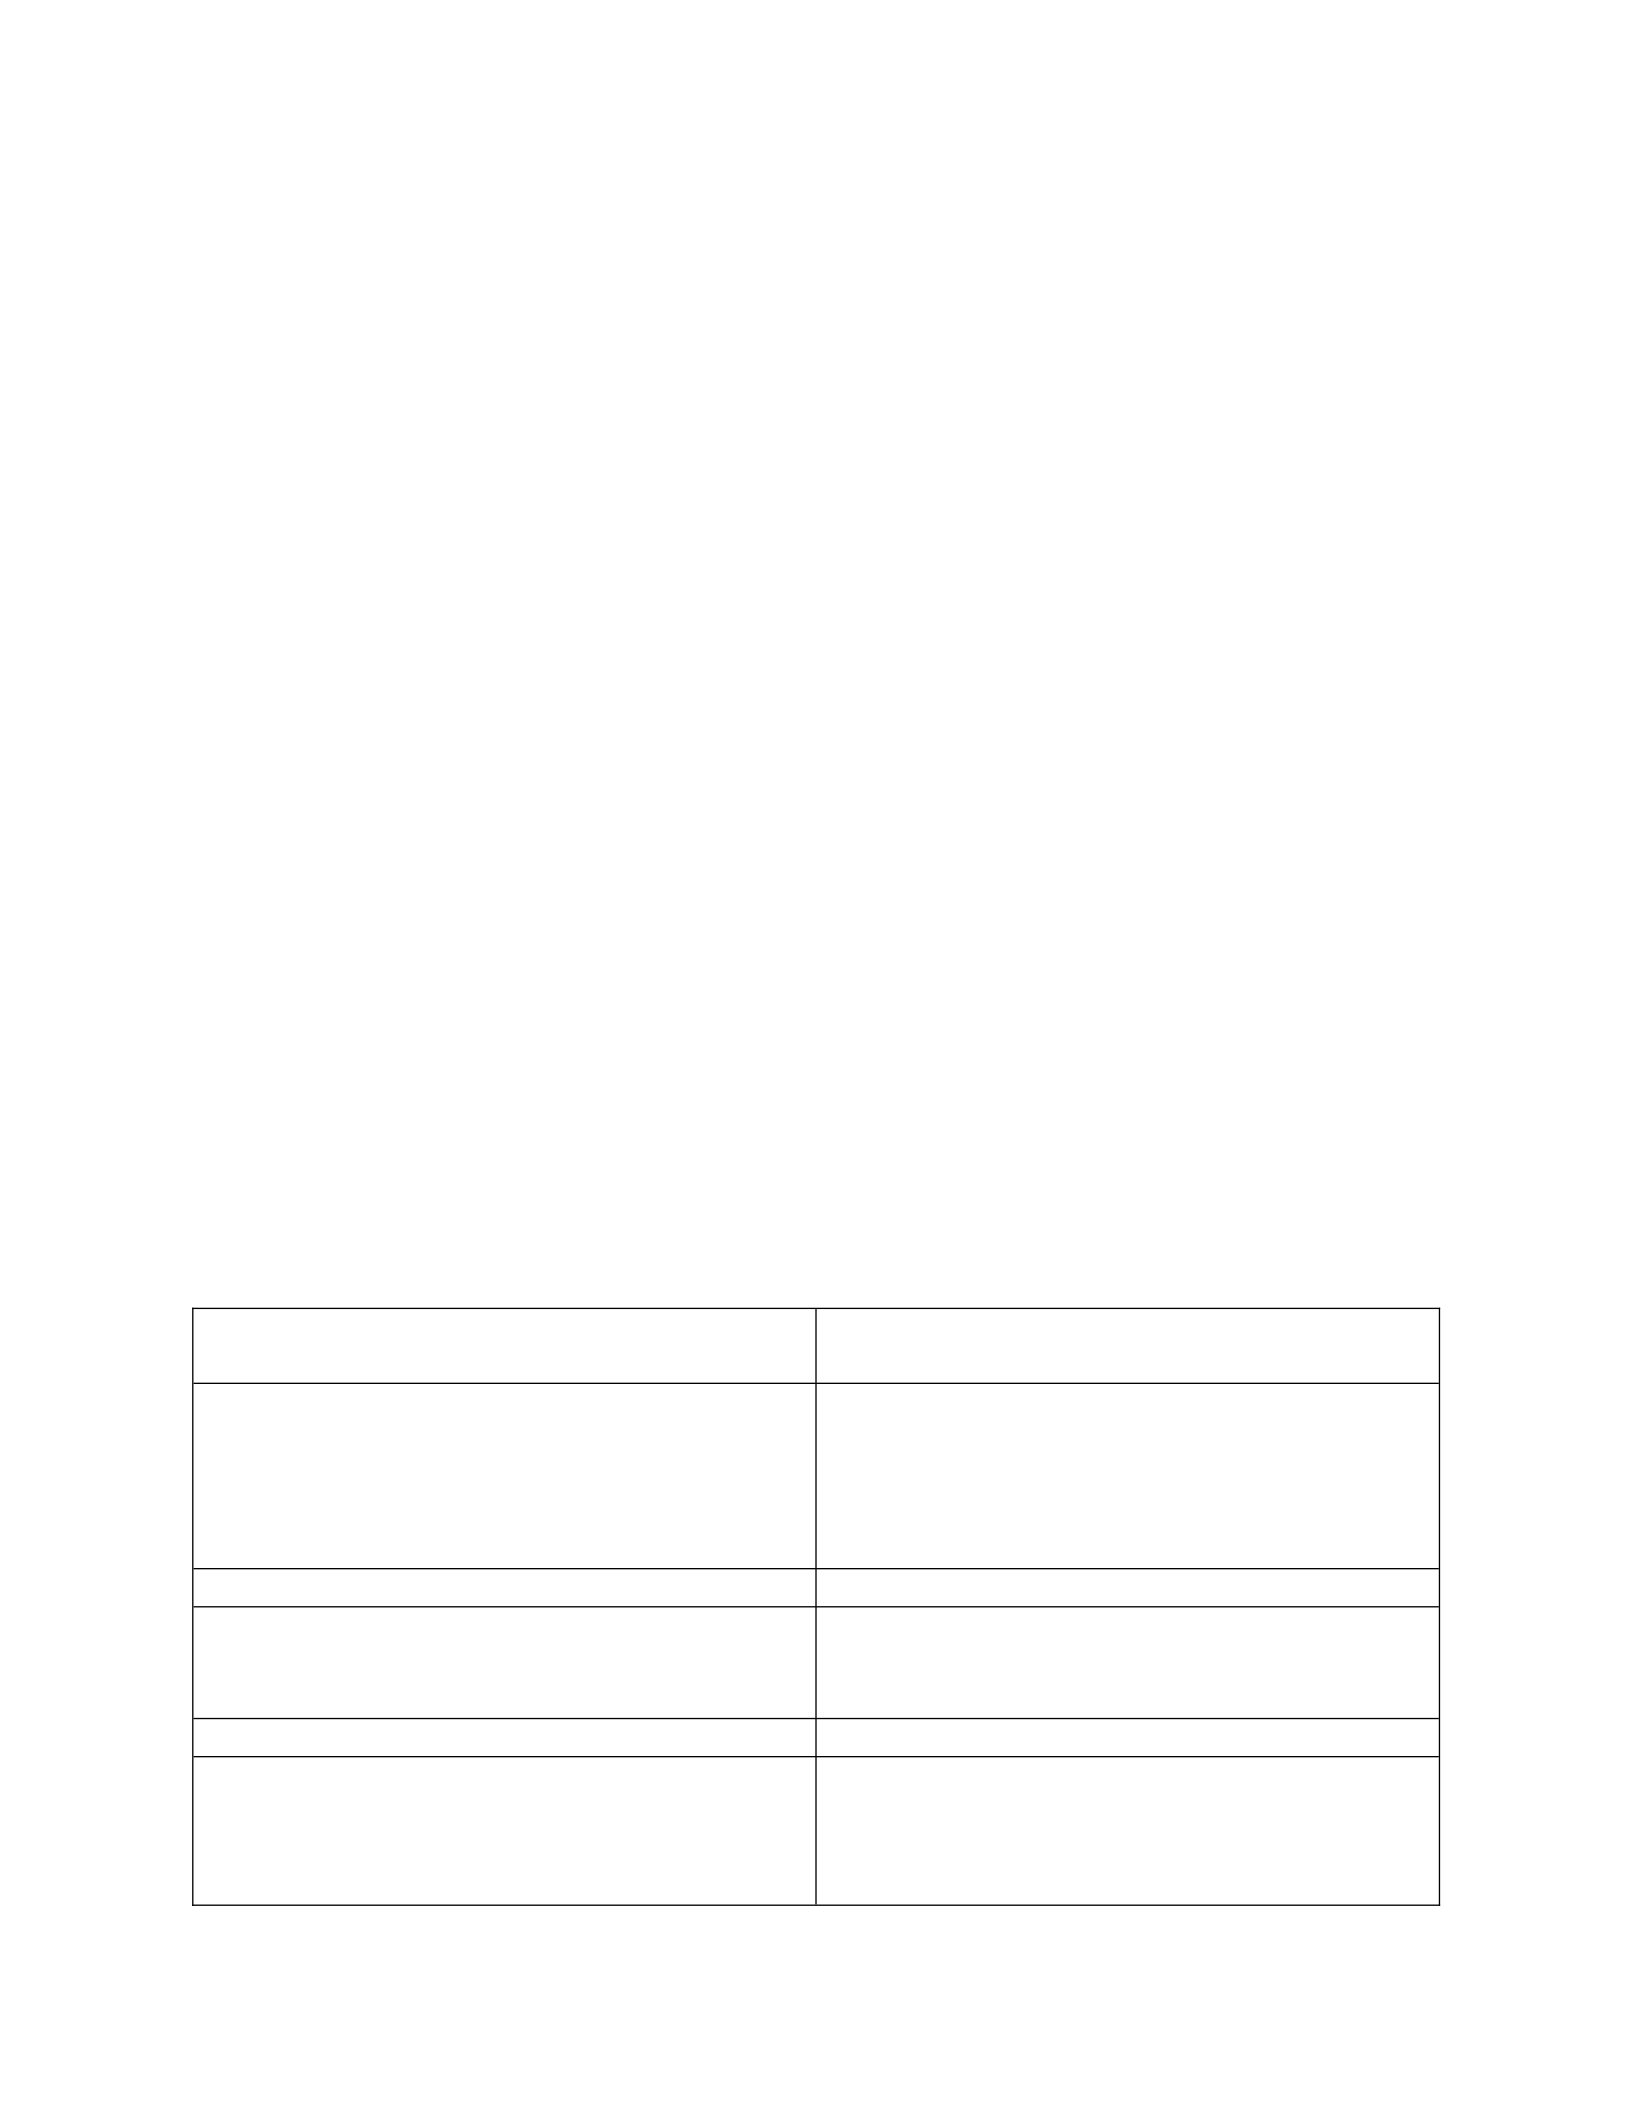
Clients Concerns
Symptoms Behaviors Stressors
Anxiety and excessive
worry
Racing thoughts, trouble
sleeping, takes about 30
minutes listing worries
Caregiving burden,
cultural expectations
Fatigue Difficulty completing tasks
and concentrating, feeling
uneasy
Unable to sleep properly
Insomnia Lays in bed worrying for
1-2hours and sleeps about
5-6hours and still wakes
worrying
Social disconnection,
finance issues, and anxiety.
Irritability and anger Snaps at family members Strained family
relationship, and money
worries
Emotional distress and
sadness
Gets sad of deceased
husband, grandkids don’t
want to talk
Ongoing feelings of
sadness and worry, social
isolation
Headaches, muscle tension
and restlessness
Worry headaches, muscle
tightness, and pacing
Caregiving demands,
retirement, grief
Alcohol use Takes 2 glasses 5day a
week
Self-medication, anxiety
management
Grief and loss Feels sad and
overwhelmed
Death of husband
Assessment
One assessment that is consistent with Amara’s presenting symptoms is the generalized
anxiety scale (GAD-7) which is a brief self-report tool that is used in screening generalized
anxiety disorder and assessing its severity. The assessment has seven measurable categories that
measures the severity of the symptoms such as excessive worry, fatigue, irritability, sleep
difficulties, and restlessness. The questions are answered on a 4 point Linkert scale ranging from
‘not at all’ to nearly every day’ (Ollendick et al., 2015). The assessment was preferred due to its
AMARA CASE STUDY ASSIGNMENT 3
ease of access and is validated across diverse populations including the older adults and helps
counselors track progress over time.
Diagnostic Impression
Based on Amara’s condition, her primary diagnostic criteria are the generalized anxiety
disorder (GAD) ICD-10 Code F41.1. This is because her symptoms are consistent with this
diagnosis as she shows more than 5symptoms including excessive worry, restlessness, fatigue,
irritability, sleep disturbance, difficulty concentrating, worry headaches, and muscle tension
which have been present for over a year (Gerlach & Gloster, 2020). Her anxiety levels have as
well impaired her daily functioning and the relationship with her grandchildren and family
members. A secondary diagnosis in this case is he adjustment disorder with mixed anxiety and
depressed mood ICD-10 Code F43.23 (American psychiatric association, 2022). This diagnosis
shows Amara’s emotional and behavioral symptoms that are in response to her identifiable
stressors.
Signs and Symptoms
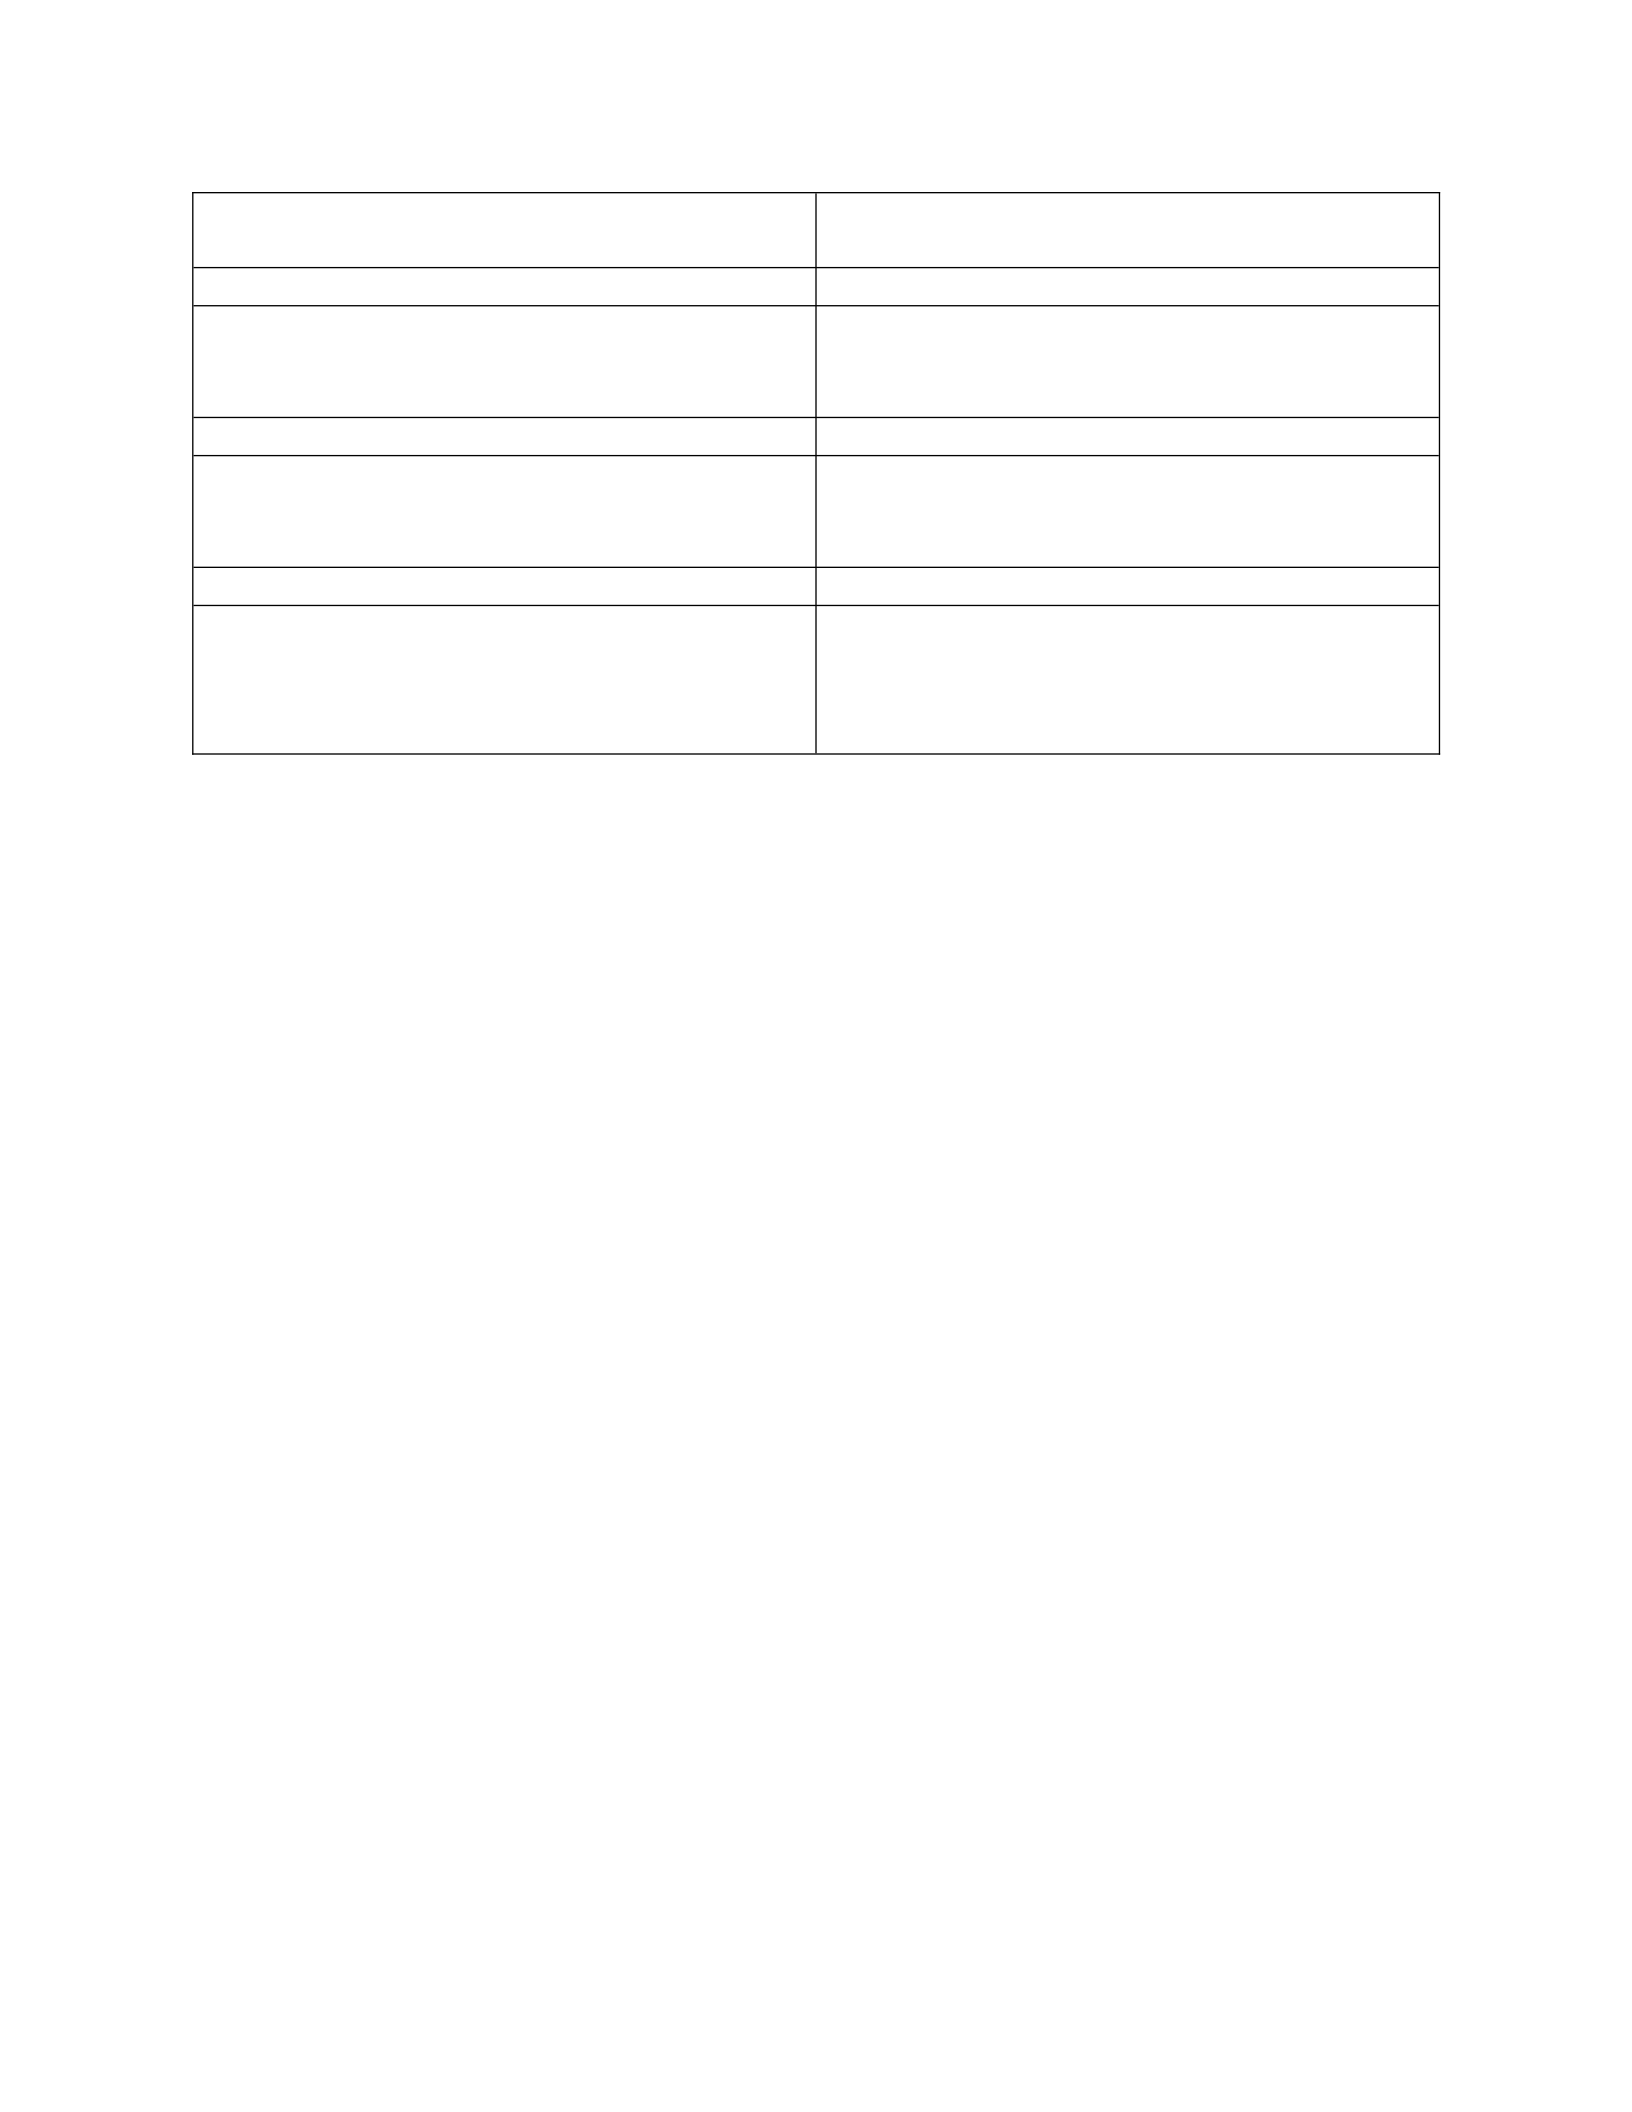
DSM-5-TR Diagnostic Criteria: Generalized
anxiety disorder(GAD) ICD-10 Code F41.1
Client’s Signs/Reported Symptoms:
Criterion A: excessive anxiety and worrying
uncontrollably
She can’t help spilling out her worries when
she talks to her family. She is worried
everyday about something and has lost
contact with friends over 18 months. She
cannot let go the thoughts in her head.
Criterion B: irritability more than usual She reports there has been more tension
between her and other family members. She
snaps at her daughter and mother.
Criterion C: restlessness, fatigue, difficulty
concentrating, muscle tension, and sleep
disturbance
Amara says she might jump out of her skin as
she is unable to relax. She is tired most of the
time, her mind races and has difficulty
concentrating, she has daily headaches, neck
AMARA CASE STUDY ASSIGNMENT 4
and shoulder tension, and struggles to fall
asleep and still wakes up early worrying.
Criterion D: emotional distress and sadness Her anxiety has harmed her relationship with
her children and grandchildren, has impacted
her daily life, and led to social isolation.
Criterion E: symptoms are not due to
substance use or a medical condition
She has no history of physical illness. Takes
Paxil to ease her anxiety but it doesn’t work
for her. Anxiety started before taking Paxil.
Criterion F: no other mental disorder explains
her anxiety.
There are no signs of major depressive
disorder, panic attacks, PTSD. She has grief
and adjustment difficulties but that doesn’t
explain her excessive worrying.
Other DSM-5-TR Conditions Considered
When reviewing Amara’s case, some other disorders that were considered due to similar
symptoms experienced included major depressive disorder (F33.9) and major depressive disorder
with anxious distress (F23.9) (American psychiatric association, 2022). Although Amara
reported she experiences sadness over her husband’s death, she is mostly fatigued, has insomnia
and has difficulties concentrating this criterion did not meet the (F33.9) because six or more
symptoms are needed to diagnose and she had only 4 of the symptoms (Black & Grant, 2014).
The F23.9 was considered due symptoms such as restlessness, difficulty concentrating, and
excessive worrying but to fit into this criterion five or more symptoms are considered and she
only had three of the symptoms.
Developmental Theories and/or Systemic Factors
Various influences such as individuals functioning, their behaviors and their well-being
affects the normal and abnormal functioning of human development. For instance, Amara has
had things that has happened in her life such as her husband being diagnosed with cancer and

AMARA CASE STUDY ASSIGNMENT 5
dying after two years, her retirement, and loss of friends. Her family member’s dynamic also
changed such as the relationship between her and her children and grandchildren. Her current
struggles can be explained through the Erik Erikson’s psychosocial theory of development
especially the stage of ego integrity vs. despair. At this late adulthood stage of 65+, people
reflect on their lives and accomplishments (Gross, 2020). If they view their experiences as
meaningful they achieve a sense of satisfaction and readiness to face life’s end. However, for
those that may feel they have fallen short they may experience despair which is marked by
bitterness, regret or fear of death.
Amara is struggling with her worries of being alone, her usefulness after retirement and if
her family will care for her in the future shows she has grown a sense of despair. Amara is also
caught up in caregiving roles since she is taking care of her 90-year-old mother. Her cultural
belief is that placing her mother in a nursing home would bring shame to the family. Priest
(2021) notes that family systems theory explains how her emotional health is tied to her
environment which is stressing her as meeting those expectations while still grieving the loss of
her husband and loss of her professional identity due to retirement has significantly contributed
to her anxiety.
Multicultural and/or Social Justice Considerations
Using the RESPECTFUL model, Amara’s ethnic/racial identity as an Asian American
woman is an important factor in considering her diagnostic process. Amara holds tightly to south
Asian cultural traditions especially in maintaining the family’s public image, respect for elders,
and family loyalty (ChenFeng & Kim, 2024). These values influence how she responds to stress,
takes her caregiving role seriously and why she delayed in seeking mental health care. Her
cultural influence does not approve of discussing personal struggles with outsiders as it is seen as

AMARA CASE STUDY ASSIGNMENT 6
unnecessary or shameful. According to Geoffrey, the Asian Americans believe that your value as
a person depends on your ability to take care of your family and community (ChenFeng & Kim,
2024). This is the reason Amara is constantly worrying of her children and grandchildren, takes
care of the mother and would not want her to go to a nursing home.
Treatment Recommendations
Key Issues for Treatment
Excessive worrying and anxiety
Relationship constraints between family and friends
Sleep disturbances and fatigue
Recommendations for Individual Counseling
Amara would benefit from cognitive behavioral therapy (CBT) as it is an evidence-based
approach used for treating generalized anxiety disorder. According to Hedman-Lagerlöf &
Axelsson (2019) CBT focuses on helping clients recognize and challenge irrational thought
patterns, develop healthier mechanisms, and learn relaxation strategies. In the case of Amara, a
counselor could introduce her to imaginal exposure technique to help her achieve a more positive
mindset by reframing her mind from the negative thoughts and compulsions to positive (Aithor,
2024). CBT targets the content of worry and uses techniques such as mindfulness exercises and
imaginal therapy in facilitating a positive mindset.
Another treatment recommendation for Amara is through the use of narrative therapy
which is a collaborative process where a counselor acts as a guide helping clients tell their stories
and identify patterns that contribute to their anxiety. Techniques that work with this treatment
option and can be helpful to Amara is guiding her to see anxiety as separate from herself,

AMARA CASE STUDY ASSIGNMENT 7
identify patterns that influence her anxiety and be able to develop strategies to challenge it, helps
her rewrite her story by identifying the strengths, values and achievements, recognize her unique
outcomes that she did and was not anxious and reconnect with her strengths, personal identity
and values that reminds her she is more capable than when she has anxious thoughts (Rockland
Recovery Behavioral Health, 2025).
Amara has excessive worry, physical tension, fatigue, difficulties concentrating, and
insomnia which makes her condition severe and chronic in nature. Hence, it is appropriate to
refer her for psychiatric medication management. Given that she had already started on Paxil
which is commonly prescribed for GAD and has not noticed any improvements after four weeks
and SSRIs takes about 6-8weeks to show full therapeutic effects, it would be important to
monitor her progress and dosage adjustment or even a medication switch under psychiatric
evaluation (Chu et al., 2018). Medication alone would not suffice but it would help relieve her
symptoms as she works towards improving with therapy.
Specific Considerations
Cultural background plays a crucial role in Amara’s decisions of care and treatment as
she openly expresses how south Asian cultural values guides her behavior. She feels it would be
a shame on her family if she allowed her mother go to a nursing home. She also stated that
counseling was not an option in her family because family problems should always be kept in the
family. Some additional information that I would need about her culture is how worry and
emotional distress are viewed in her family or community and what are the expectations of
caregiving in her cultural tradition. Since she was born in the United States after two years since
her parents immigrated, I would also want to know how much of the westernized views she has

AMARA CASE STUDY ASSIGNMENT 8
accepted and which traditional values she still holds. Knowing her specific Hindu practices that
she cherishes might as well serve as emotional support.
Some kinds of values conflict that I might experience due to the client’s culture is
seeking help when experiencing symptoms of a mental health disorder. While Amara seeks
counseling and therapy as a last resort since she would love to maintain her bond with family I
would opt to seek it first instance I notice emotional distress. I believe once I am well mentally,
physically, and psychologically that’s when I can take care of another person without weighing
on them my emotional burden. Managing my personal values with Amara would involve
practicing client-centered care, cultural humility and acknowledge that what seems clinically
helpful may not align with her worldview. This could include helping her cope with emotional
distress instead of challenging her caregiving role.
AMARA CASE STUDY ASSIGNMENT 9
References
Aithor. (2024, April 11). Cognitive behavior therapy and narrative approach. aithor.com.
https://aithor.com/essay-examples/cognitive-behavior-therapy-and-narrative-
approach
American psychiatric association. (2022). Alphabetical listing of DSM-5 diagnoses and
codes (ICD-9-CM and ICD-10-CM). Diagnostic and Statistical Manual of Mental
Disorders, 5th Edition. https://doi.org/10.1176/appi.books.9780890425596.744130
Black,HD.HW., & Grant,HJ.HE. (2014). DSM-5® guidebook: The essential companion to the
diagnostic and statistical manual of mental disorders (5thHed.). American Psychiatric
Pub.
ChenFeng,HJ., & Kim,HL. (2024). Asian American identities, relationships, and post-
migration legacies: Reflections from marriage and family therapists. Taylor &
Francis.
Chu,HJ., Batchelder,HH., & Poon,HG. (2018). Cognitive behavioral models, measures, and
treatments for stress disorders in Asian Americans. Treating depression, anxiety, and
stress in ethnic and racial groups: Cognitive behavioral approaches, 229-262.
https://doi.org/10.1037/0000091-010
Gerlach,HA., & Gloster,HA. (2020). Generalized anxiety disorder and worrying: A
comprehensive handbook for clinicians and researchers. John Wiley & Sons.
Gross,HY. (2020). Erikson's stages of psychosocial development. The Wiley Encyclopedia of
Personality and Individual Differences, 179-184.
https://doi.org/10.1002/9781118970843.ch31

AMARA CASE STUDY ASSIGNMENT 10
Hedman-Lagerlöf,HE., & Axelsson,HE. (2019). Cognitive behavioral therapy for health
anxiety. The Clinician's Guide to Treating Health Anxiety, 79-122.
https://doi.org/10.1016/b978-0-12-811806-1.00006-8
Ollendick,HT.HH., Jarrett,HM.HA., White,HB.HA., White,HS.HW., & Grills,HA.HE. (2015). Primary
versus secondary diagnosis of generalized anxiety disorder in youth: Is the distinction
an important one? Child Psychiatry & Human Development, 47(4), 548-553.
https://doi.org/10.1007/s10578-015-0588-1
Priest,HJ.HB. (2021). Family systems theory and family therapy models. The Science of
Family Systems Theory, 131-139. https://doi.org/10.4324/9780367854591-14
Rockland Recovery Behavioral Health. (2025, January 20). How narrative therapy can help
anxiety. https://rocklandrecoverybh.com/behavioral-health-blog/how-narrative-
therapy-can-help-anxiety/

