



CASE STUDY JEFF 2
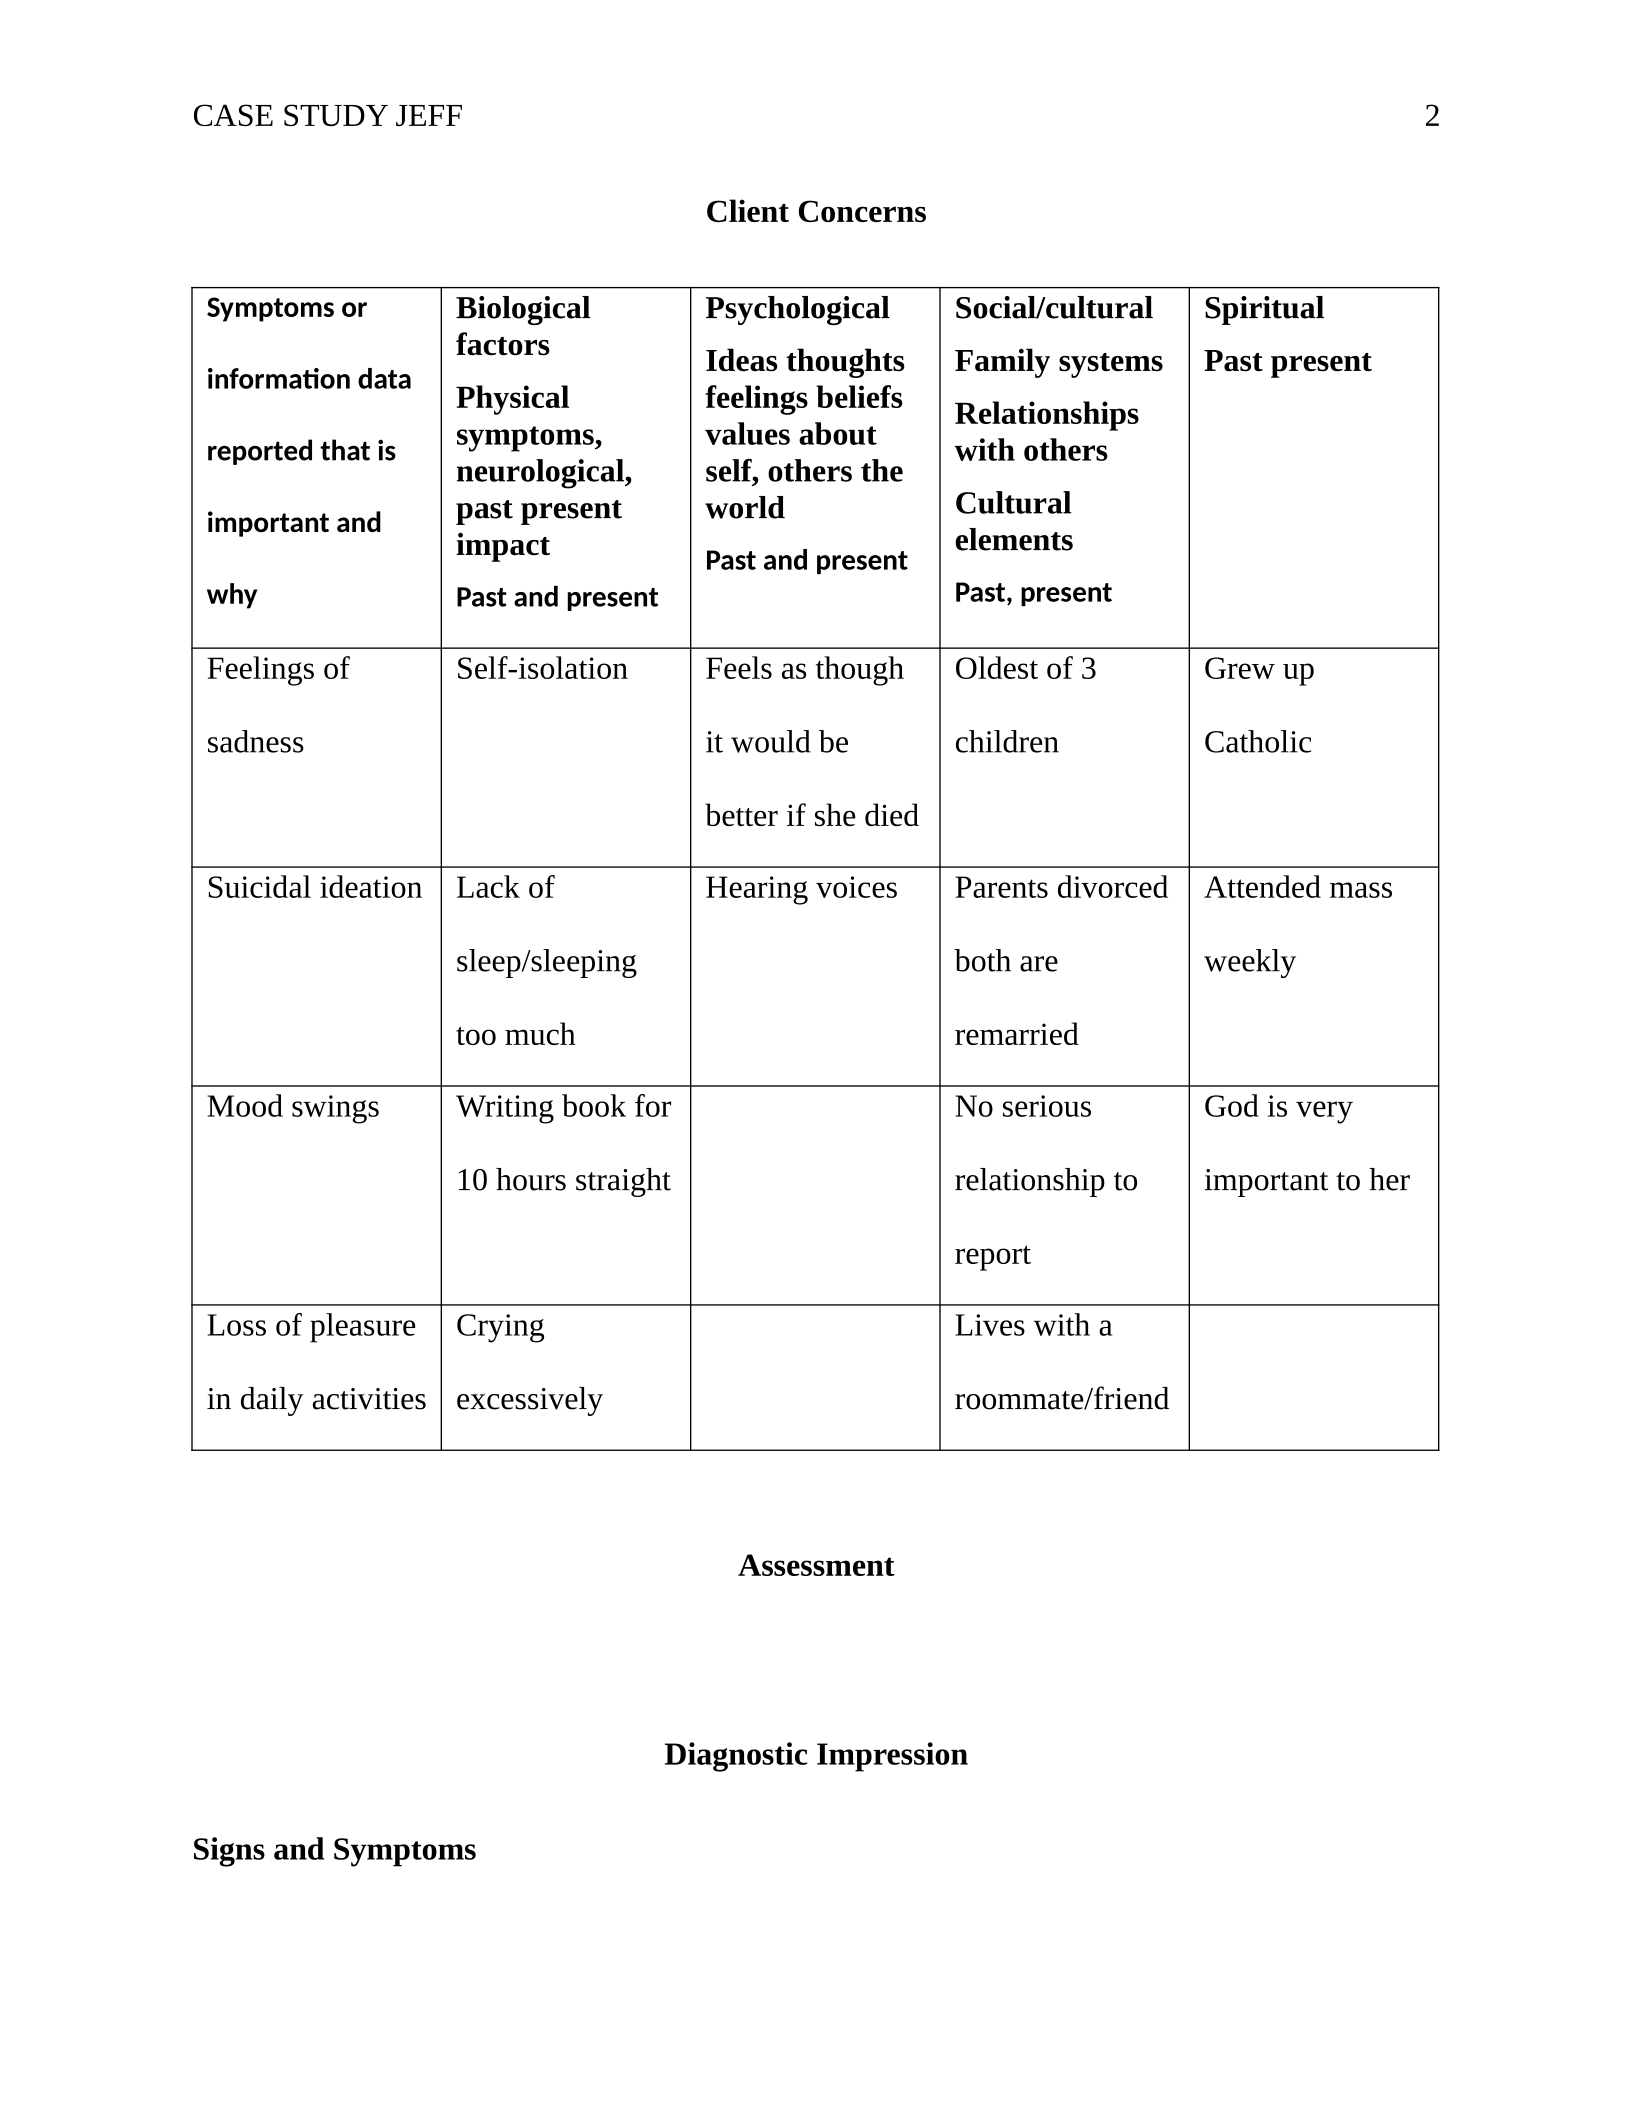
Client Concerns
Symptoms or
information data
reported that is
important and
why
Biological
factors
Physical
symptoms,
neurological,
past present
impact
Past and present
Psychological
Ideas thoughts
feelings beliefs
values about
self, others the
world
Past and present
Social/cultural
Family systems
Relationships
with others
Cultural
elements
Past, present
Spiritual
Past present
Feelings of
sadness
Self-isolation Feels as though
it would be
better if she died
Oldest of 3
children
Grew up
Catholic
Suicidal ideation Lack of
sleep/sleeping
too much
Hearing voices Parents divorced
both are
remarried
Attended mass
weekly
Mood swings Writing book for
10 hours straight
No serious
relationship to
report
God is very
important to her
Loss of pleasure
in daily activities
Crying
excessively
Lives with a
roommate/friend
Assessment
Diagnostic Impression
Signs and Symptoms
CASE STUDY JEFF 3
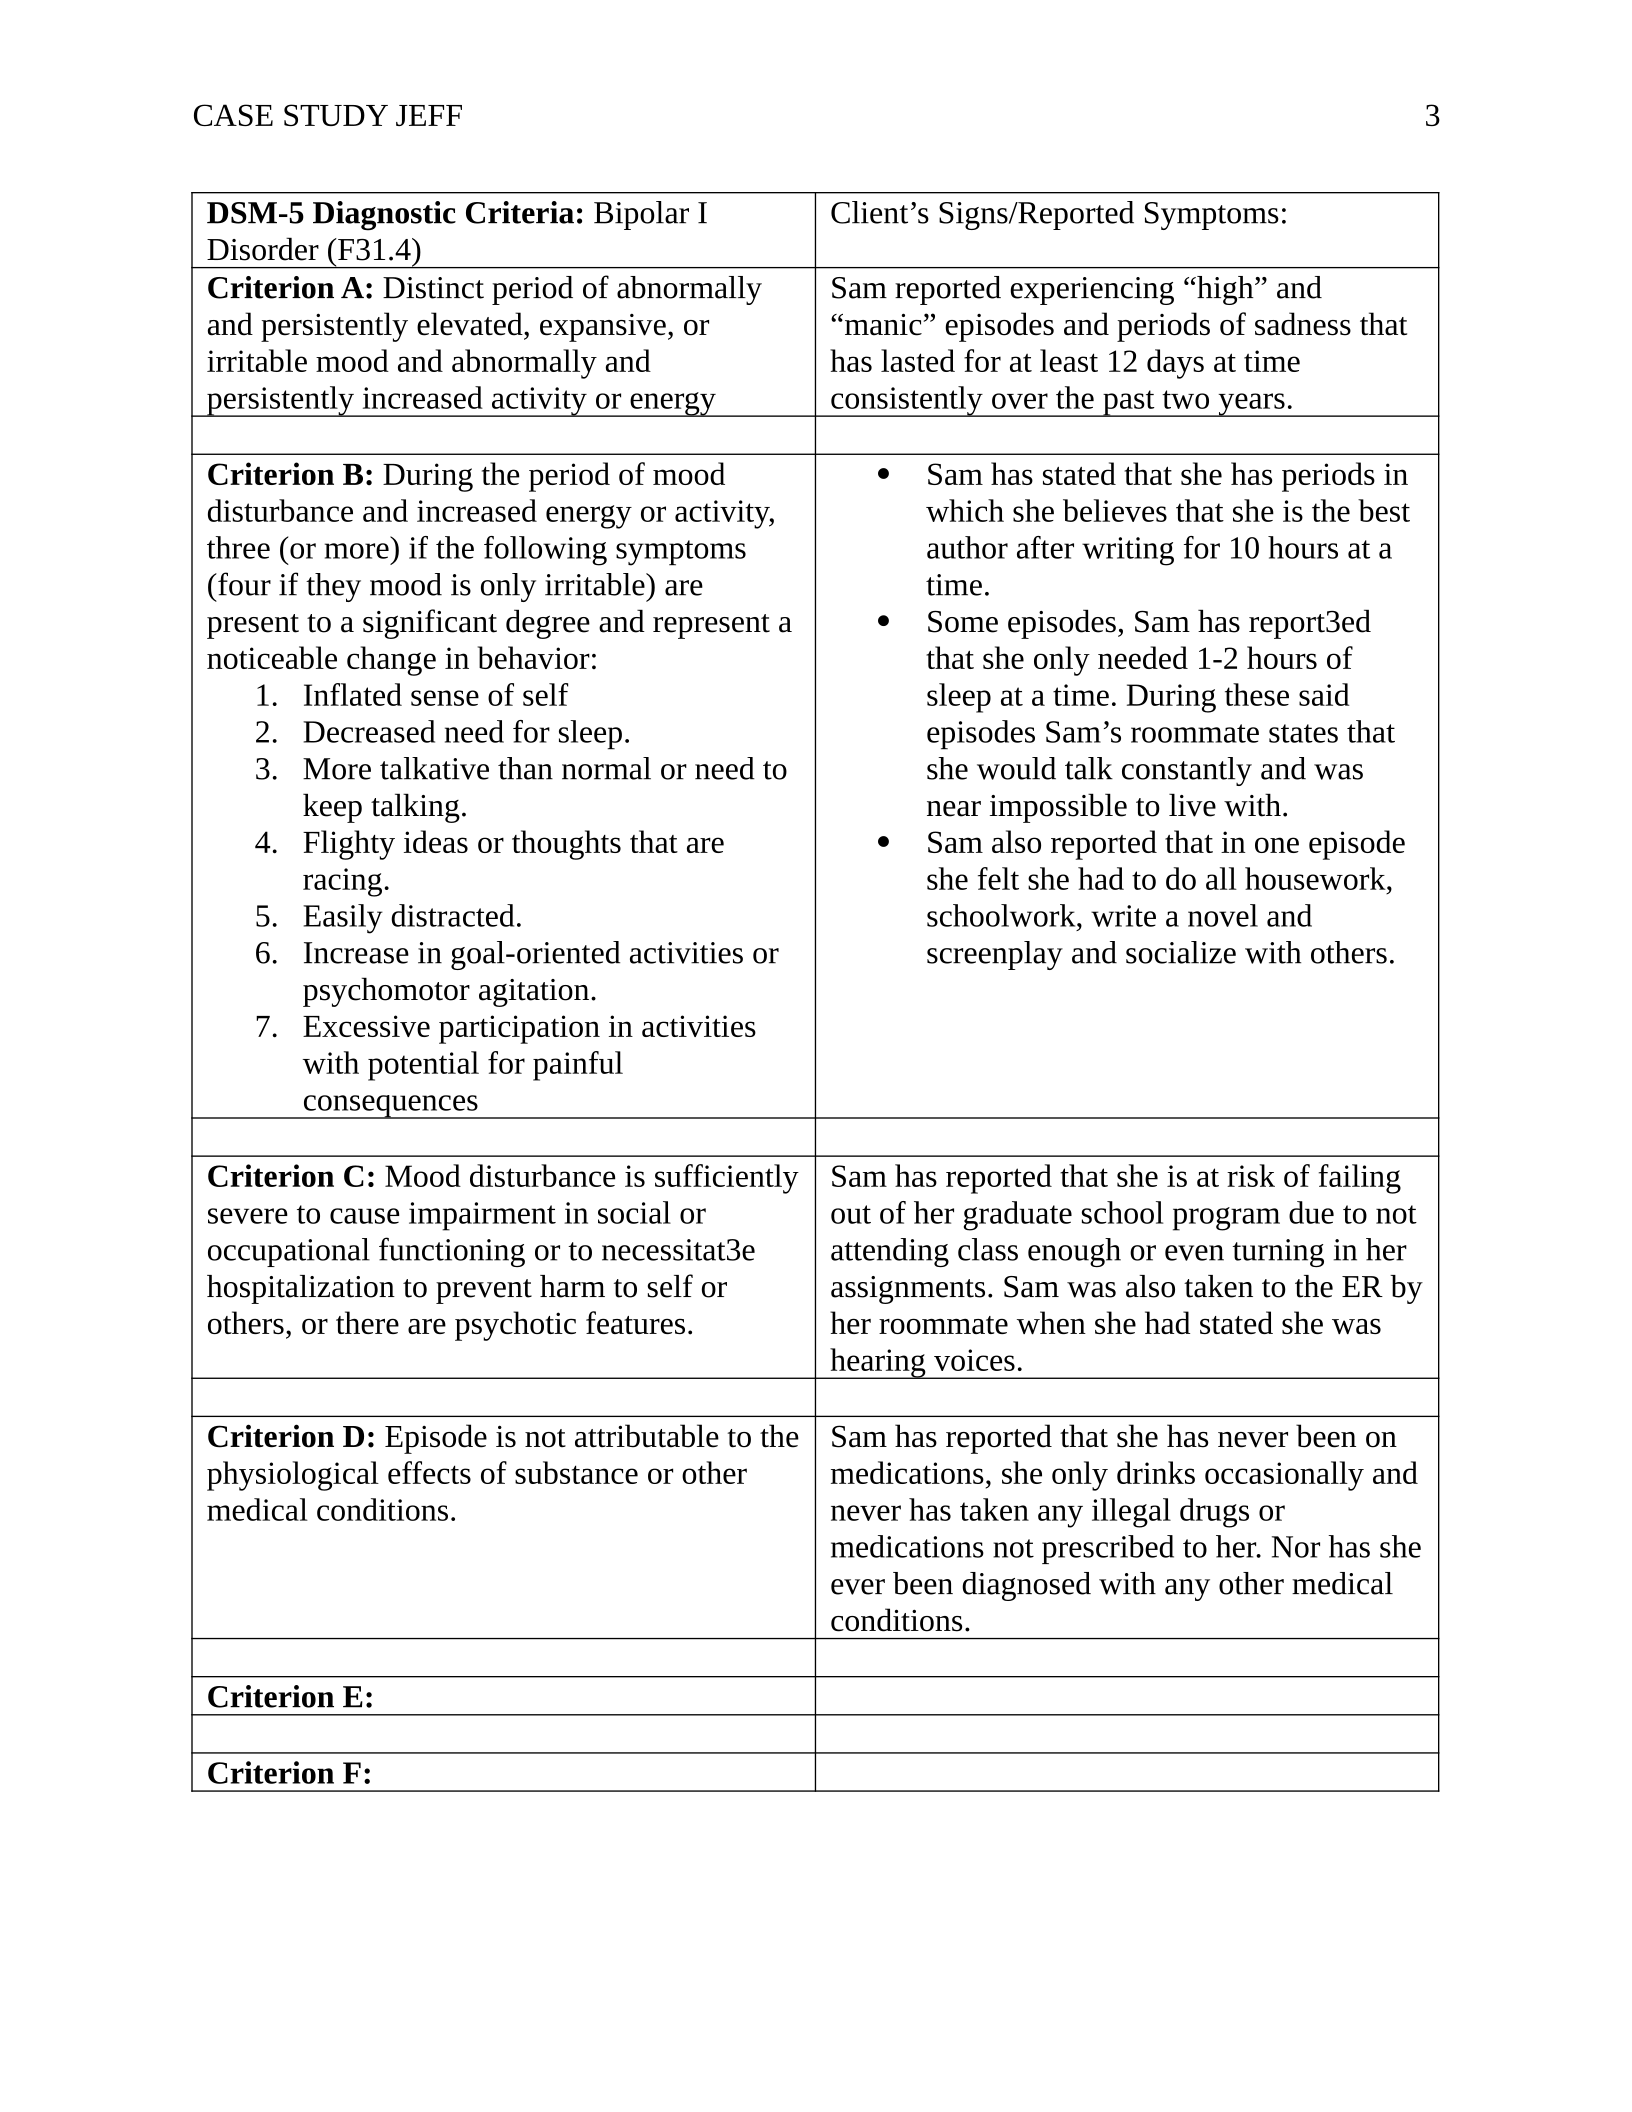
DSM-5 Diagnostic Criteria: Bipolar I
Disorder (F31.4)
Client’s Signs/Reported Symptoms:
Criterion A: Distinct period of abnormally
and persistently elevated, expansive, or
irritable mood and abnormally and
persistently increased activity or energy
Sam reported experiencing “high” and
“manic” episodes and periods of sadness that
has lasted for at least 12 days at time
consistently over the past two years.
Criterion B: During the period of mood
disturbance and increased energy or activity,
three (or more) if the following symptoms
(four if they mood is only irritable) are
present to a significant degree and represent a
noticeable change in behavior:
1. Inflated sense of self
2. Decreased need for sleep.
3. More talkative than normal or need to
keep talking.
4. Flighty ideas or thoughts that are
racing.
5. Easily distracted.
6. Increase in goal-oriented activities or
psychomotor agitation.
7. Excessive participation in activities
with potential for painful
consequences
Sam has stated that she has periods in
which she believes that she is the best
author after writing for 10 hours at a
time.
Some episodes, Sam has report3ed
that she only needed 1-2 hours of
sleep at a time. During these said
episodes Sam’s roommate states that
she would talk constantly and was
near impossible to live with.
Sam also reported that in one episode
she felt she had to do all housework,
schoolwork, write a novel and
screenplay and socialize with others.
Criterion C: Mood disturbance is sufficiently
severe to cause impairment in social or
occupational functioning or to necessitat3e
hospitalization to prevent harm to self or
others, or there are psychotic features.
Sam has reported that she is at risk of failing
out of her graduate school program due to not
attending class enough or even turning in her
assignments. Sam was also taken to the ER by
her roommate when she had stated she was
hearing voices.
Criterion D: Episode is not attributable to the
physiological effects of substance or other
medical conditions.
Sam has reported that she has never been on
medications, she only drinks occasionally and
never has taken any illegal drugs or
medications not prescribed to her. Nor has she
ever been diagnosed with any other medical
conditions.
Criterion E:
Criterion F:

CASE STUDY JEFF 4
Other DSM-5 Conditions to Consider
Developmental Theories and/or Systemic Factors
Multicultural and/or Social Justice Considerations
Treatment Recommendations
Key Issues for Treatment
Recommendations for Individual Counseling
Specific Considerations
Sam – Case Study 2: How does a client being in crisis change the focus of your assessment and
treatment planning? How might a client being in crisis affect a diagnosis?
When dealing with a client that is actively in a crisis it is important for the counselor to
recognize what the client is presenting with and then plan accordingly to help the client through
the crisis moment. Understanding that when a client such as Sam is in a crisis their psychological
state may be altered and this must be addressed immediately before moving forward. With a
client in crisis if you try to come up with a diagnosis and treatment plan before the crisis is
addressed, you may not get an accurate diagnosis or treatment plan which would be counter
productive to the client.

CASE STUDY JEFF 6
References
American Psychiatric Association. (2022). Diagnostic and statistical manual of mental disorders
(5th ed., text rev.).
Henken, H. T., Kupka, R. W., Draisma, S., Lobbestael, J., van den Berg, K., Demacker, S. M. A.,
& Regeer, E. J. (2020). A cognitive behavioural group therapy for bipolar disorder using
daily mood monitoring. Behavioural and Cognitive Psychotherapy, 48(5), 515-529.
https://doi.org/10.1017/S1352465820000259
Lang, D., Cone, N., Clark-Plaskie, M., Overstreet, L., Lally, M., & Valentine-French, S. (2022,
August 1). Psychosocial development in early adulthood. Individual and Family
Development Health and Wellbeing.
https://iastate.pressbooks.pub/individualfamilydevelopment/chapter/psychosocial-
development-in-emerging-adulthood/#:~:text=Erikson’s%20Theory&text=Erikson
%20believed%20that%20the%20main,self%20without%20losing%20one’s%20self.
Wright, K., Dodd, A., Warren, F. C., Medina-Lara, A., Taylor, R., Jones, S., Owens, C., Javaid,
M., Dunn, B., Harvey, J. E., Newbold, A., & Lynch, T. (2018). The clinical and cost
effectiveness of adapted dialectical behaviour therapy (DBT) for bipolar mood instability
in primary care (ThrIVe-B programme): A feasibility study. Current Controlled Trials in
Cardiovascular Medicine, 19(1), 560-560. https://doi.org/10.1186/s13063-018-2926-7
Powered by TCPDF (www.tcpdf.org)

