


CASE STUDY: JEFF 1
Case Study: Jeff
Destinee Chavis
School of Behavioral Science, Liberty University
Author Note
Destinee Chavis
I have no known conflict of interest to disclose.
Correspondence concerning this article should be addressed to Destinee Chavis
Email: dmchavis1@liberty.edu
CASE STUDY: JEFF 2
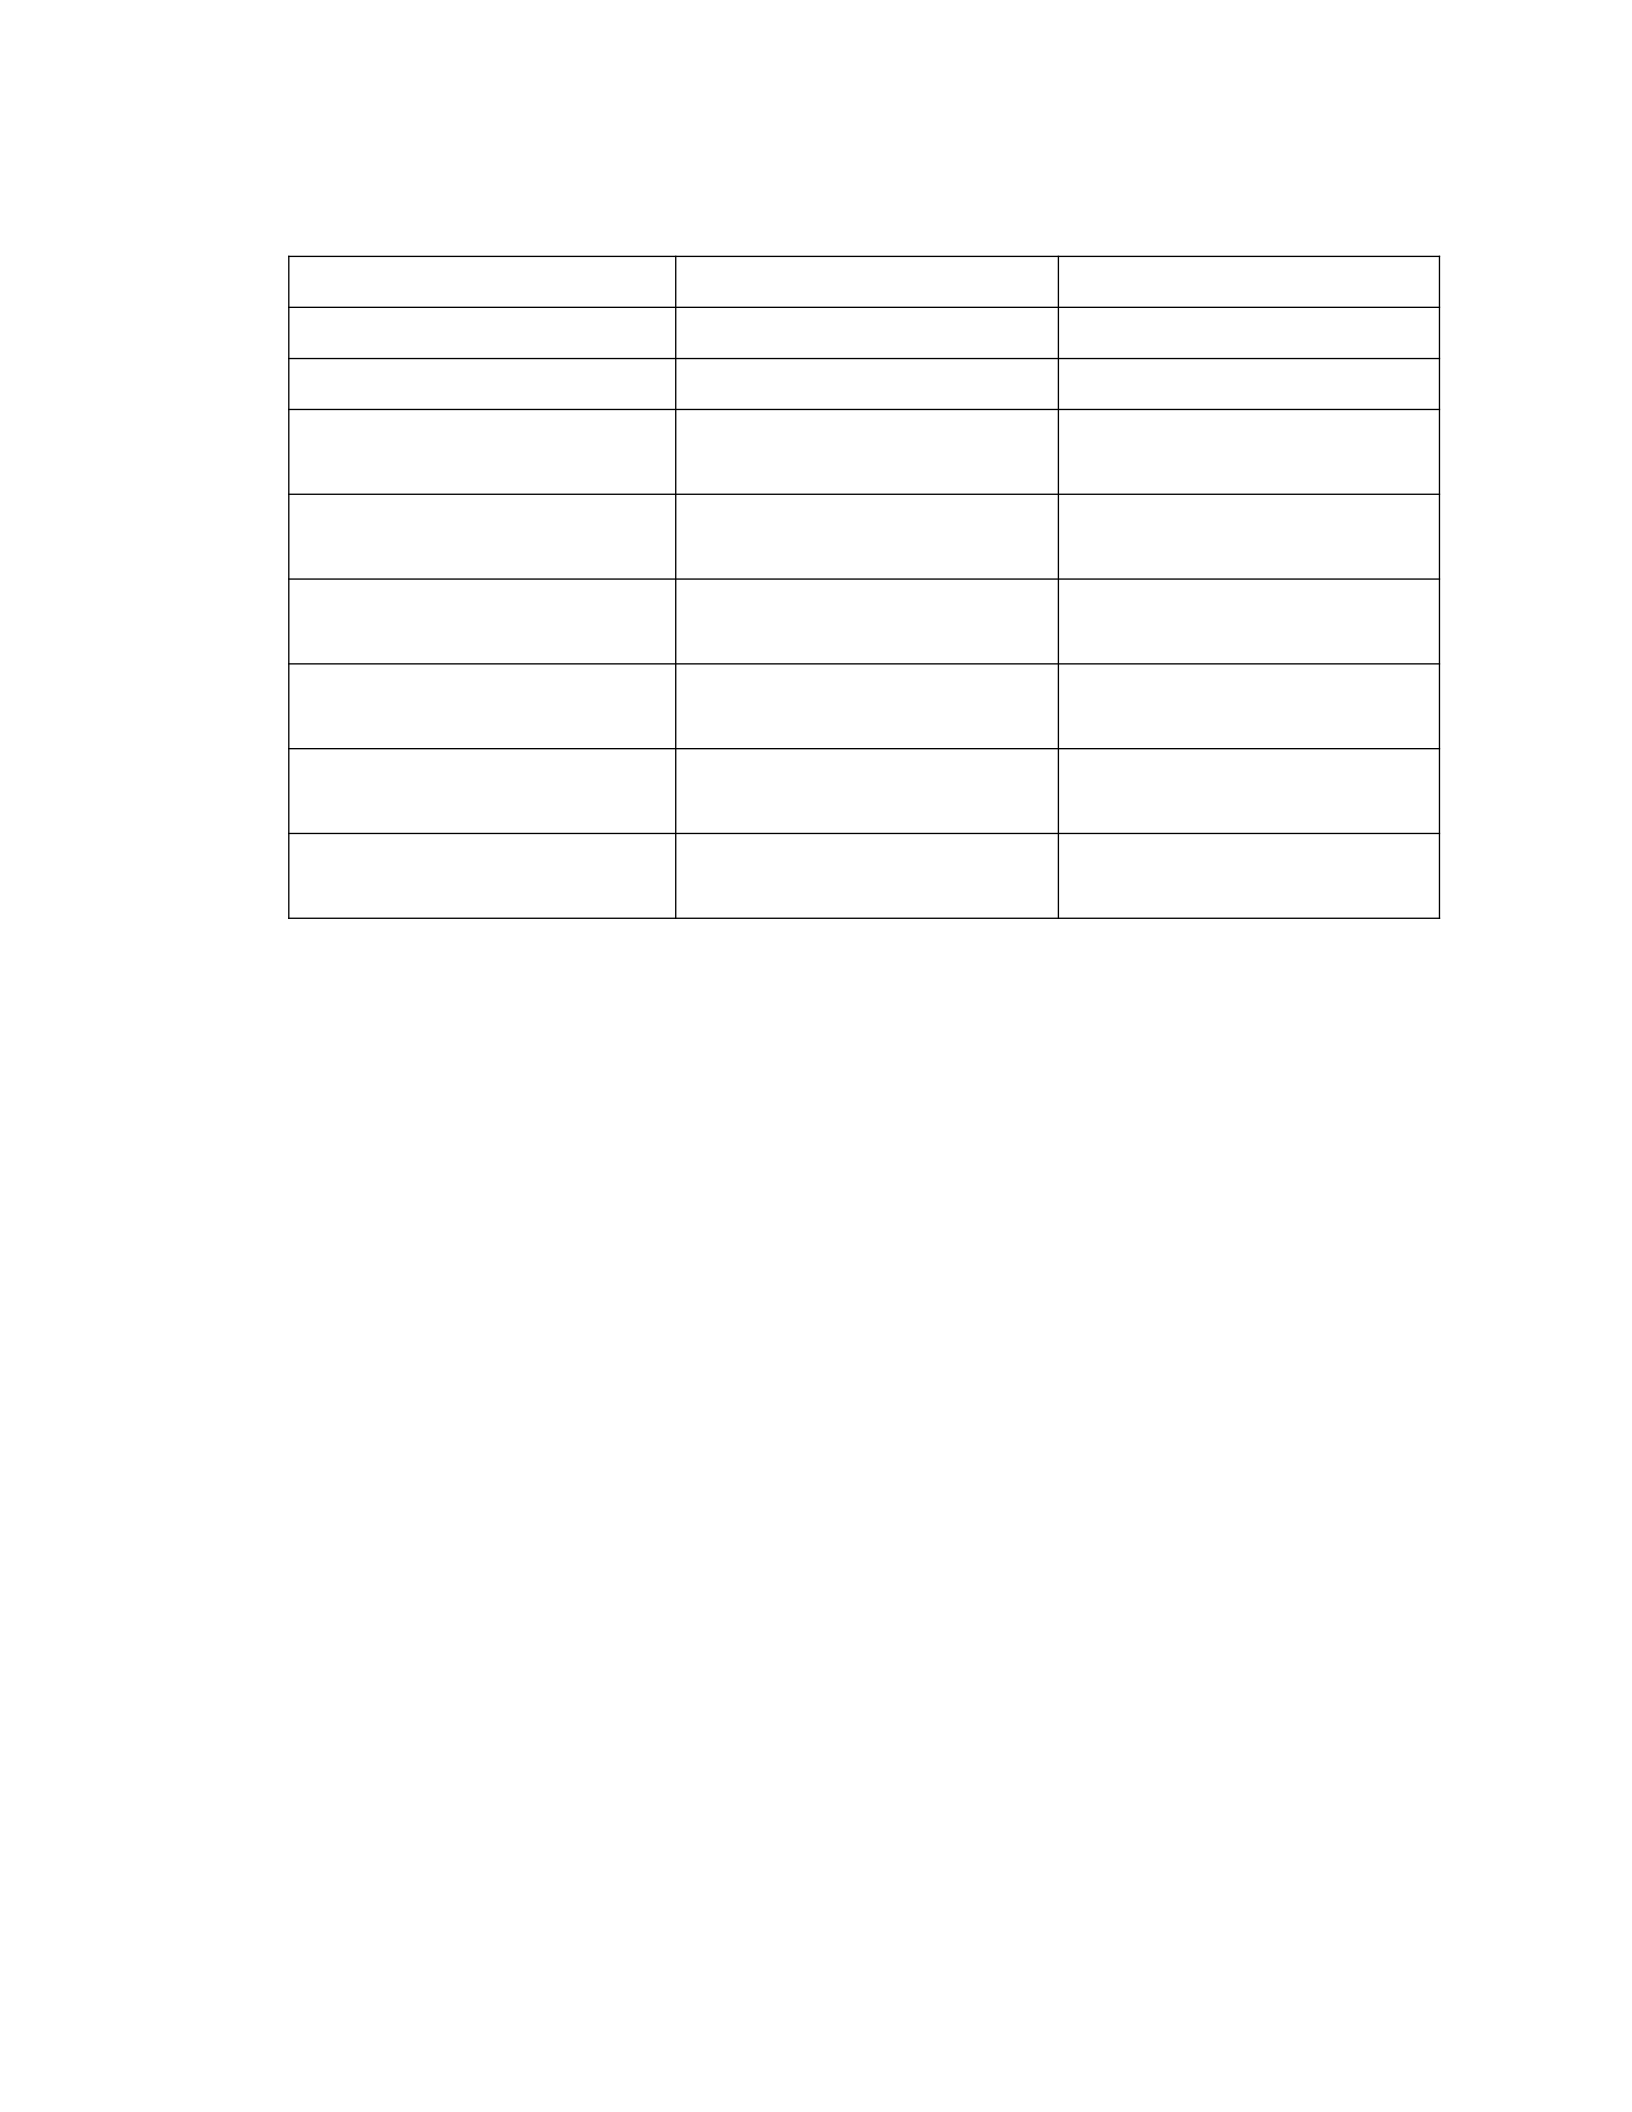
Client Concerns
Symptoms Behaviors Stressors
Sadness episodes Showing up late for work Divorce
Fatigue Intense hangovers Risk of being fired
Low to no appetite Domestic violence with his
ex-wife
Estranged relationship with
his kids and favorite brother
Irritability Isolation from family and
friends
Legal history
Aggression Arrests leading to DUI
charges and jail time
Increased alcohol
consumption due to cravings
Positive alcohol tests
Suicidal Ideations Leaving work to drink with
friends
.
Increased tolerance for
alcohol
Assessment
To accurately assess Jeff’s case, the clinician could benefit from using the AUDIT
assessment. The Alcohol Use Disorders Identification Test is a 10-question screening tool that
was developed by the World Health Organization (WHO), to assess alcohol consumption,
drinking behaviors, and alcohol related problems (Saunders et al., 1993). This assessment would
be effective in identifying harmful patterns in Jeff’s case, differentiating between abuse and
dependency, and helping the clinician formally decide on a DSM-5 diagnosis.
Diagnostic Impression
Based on the interview provided, the clinician can identify both a primary and secondary
diagnosis for Jeff’s case. His symptoms and history strongly support the diagnosis of F10.20
Alcohol Use Disorder, Severe, without Perceptual Disturbance. The secondary diagnosis
considered is, F33.1 Major Depressive Disorder, Recurrent, Moderate. According to the DSM-5
CASE STUDY: JEFF 3
Jeff meets numerous criteria for Alcohol Use Disorders. Since his divorce, Jeff’s drinking has
escalated, and he continues to drink despite facing severe consequences if he continues to use it.
He also presents with symptoms that a consistent with Major Depressive Disorder. During his
interview, Jeff reported that he has experienced several periods of prolonged sadness, lasting 7-8
months. Even when the depressive symptoms subside, Jeff states he still feels underlying
sadness. One diagnosis that was considered but ruled out was Generalized Anxiety Disorder. If
Jeff presented chronic worrying or tension beyond depressive symptoms then this diagnosis
would be appropriate.
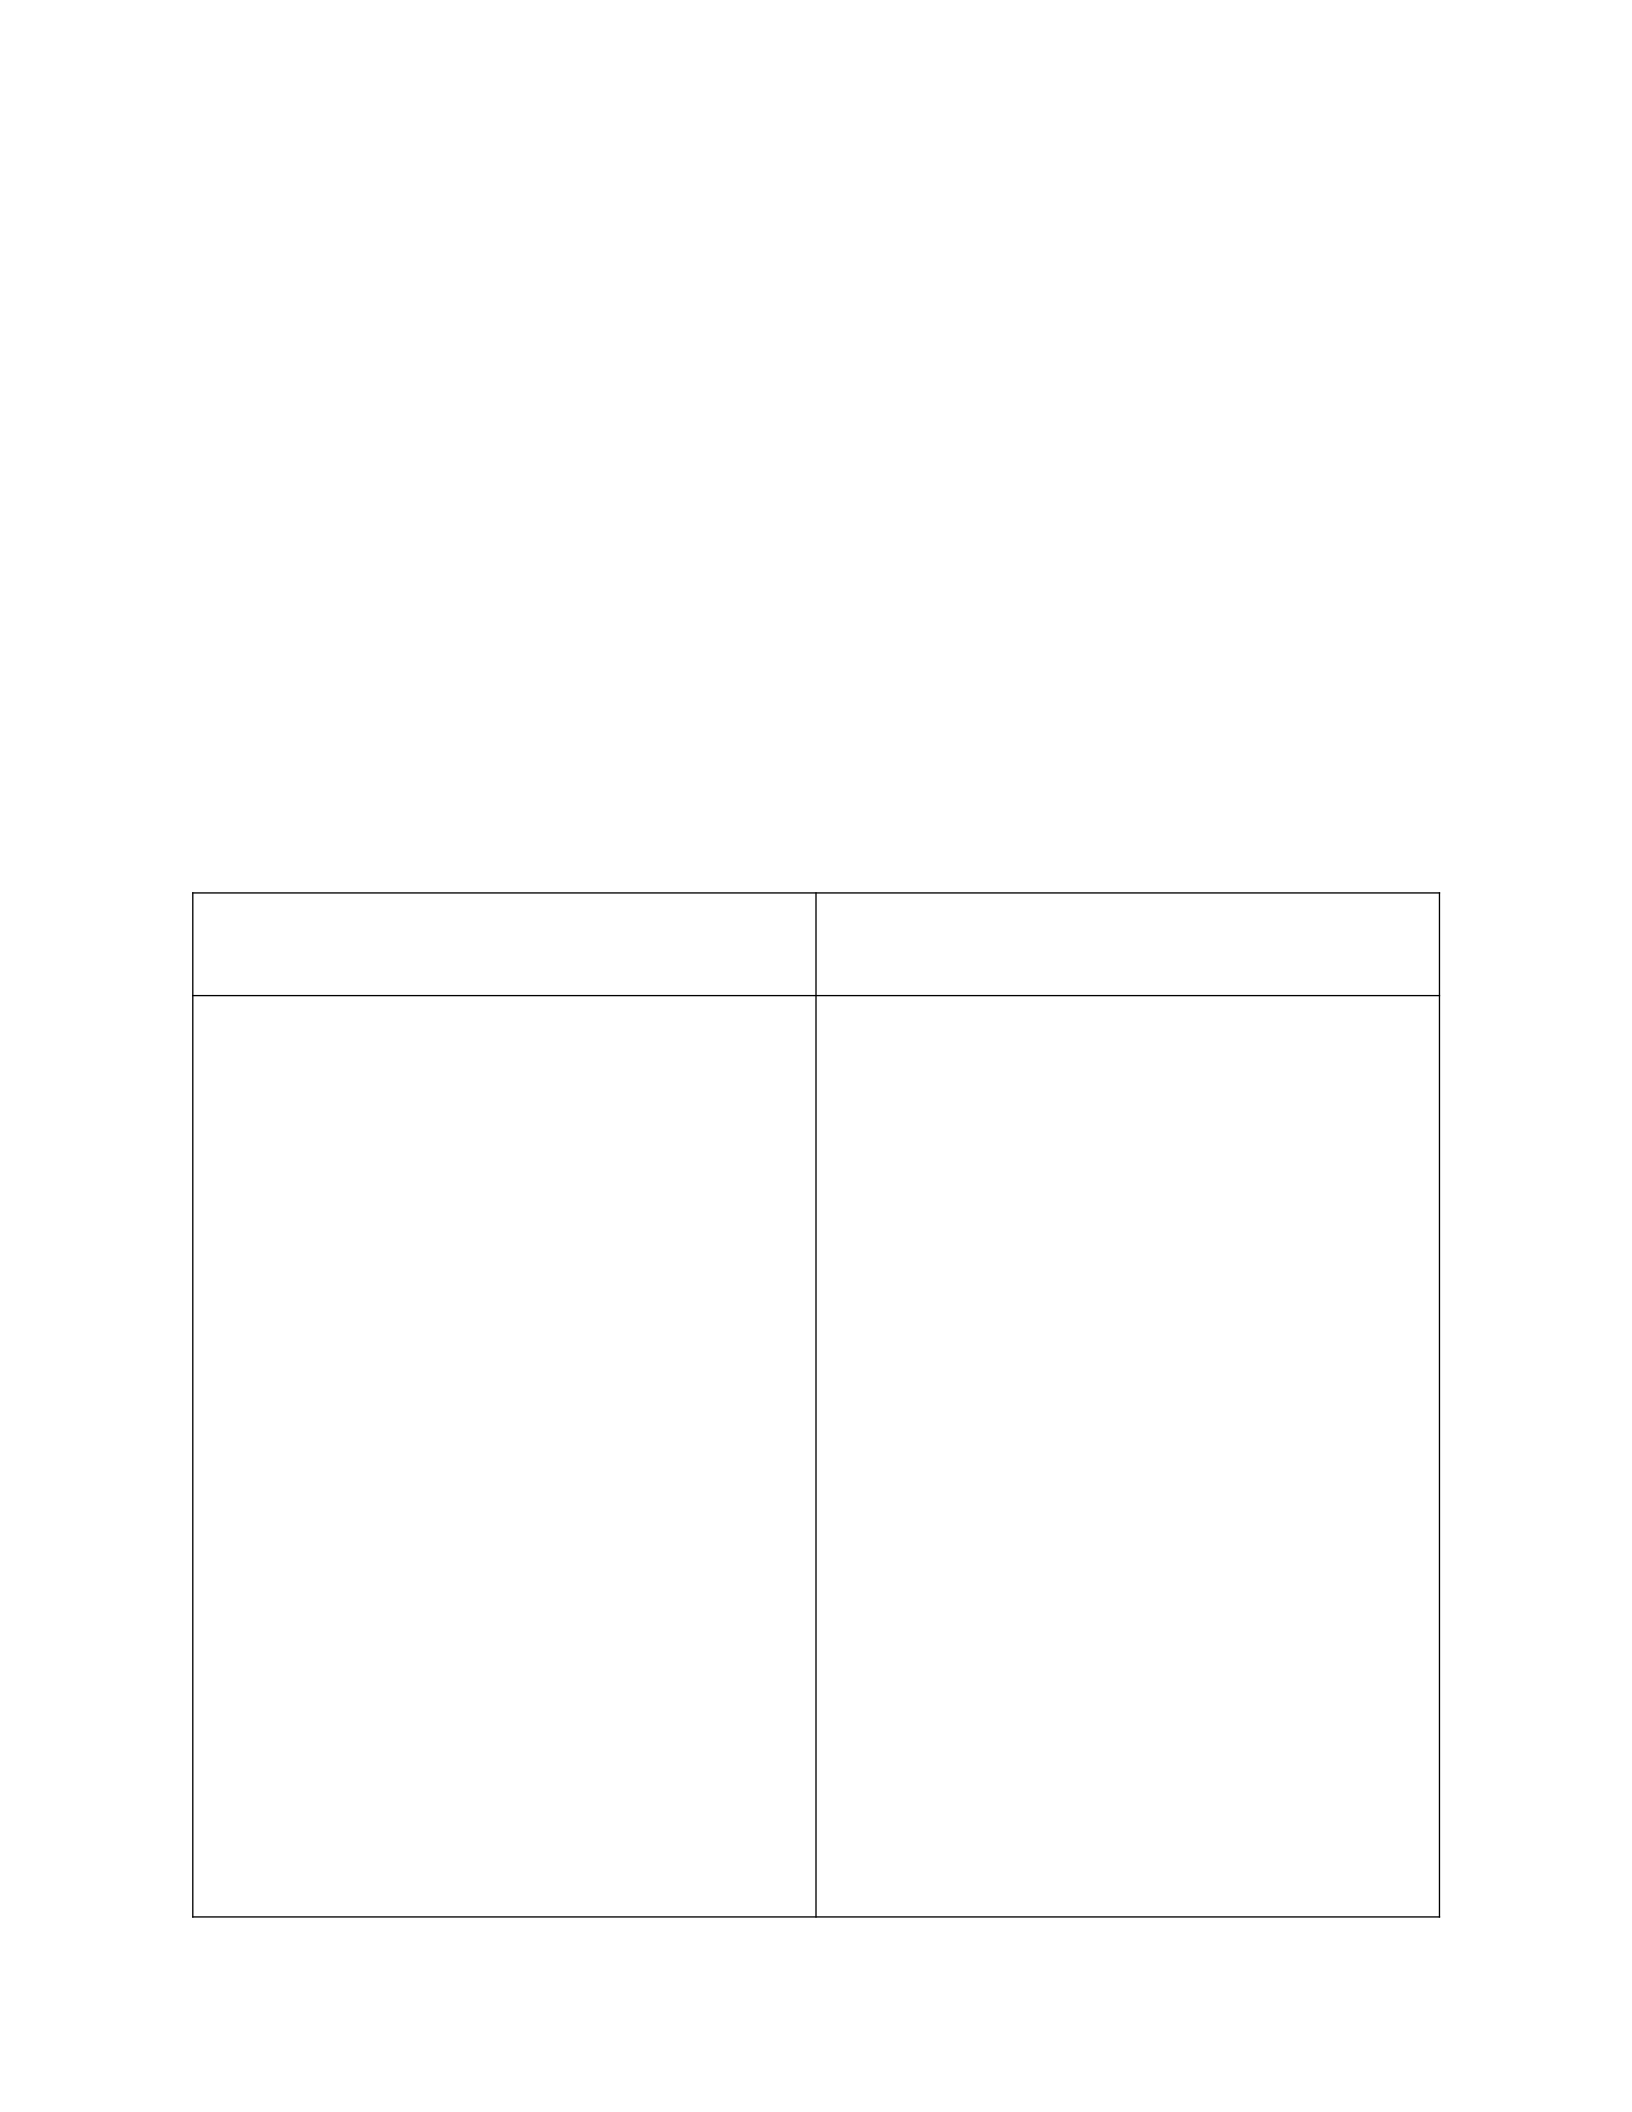
Signs and Symptoms
DSM-5-TR Diagnostic Criteria of: F10.20
Alcohol Use Disorder, Severe, without
perceptual disturbances
Client’s Signs/Reported Symptoms:
Criterion A: A problematic pattern of alcohol use
leading to clinically significant impairment or
distress, as manifested by at least two of the
following, occurring within a 12-month period:
1.Alcohol is often taken in larger amounts or
over a longer period than was intended.
2. There is a persistent desire or unsuccessful
efforts to cut down or control alcohol use.
3. A great deal of time is spent in activities
necessary to obtain alcohol, use alcohol, or
recover from its effects.
4. Craving, or a strong desire or urge to use
alcohol.
5. Recurrent alcohol use resulting in a failure
to fulfill major role obligations at work,
school, or home.
6. Continued alcohol use despite having
persistent or recurrent social or interpersonal
problems caused or exacerbated by the effects
of alcohol.
7. Important social, occupational, or
recreational activities are given up or reduced
because of alcohol use.
8. Recurrent alcohol use in situations in which
it is physically hazardous.
9. Alcohol use is continued despite
knowledge of having a persistent or recurrent
A1. Jeff drinks daily; he has admitted to
escalating use and increased tolerance.
A2. He attempted treatment to repair the
relationship with his wife but quit going and
did not reduce alcohol consumption.
A3. Jeff spends his free time drinking or
recovering from hangovers.
A4. Clients admit to having strong cravings,
especially after 10 or more hours of working.
A5. Client is often late for work; he has
received multiple write-ups and suspensions.
He is at risk of losing his job.
A6. Drinking contributed to domestic
violence with his ex-wife and ultimately
divorce.
A7. He avoids seeing his children and seeking
social support systems.
A8: He has driven under the influence.
resulting in DUI’s and overnights in jail
A9. Client admits alcohol may contribute to
his depression, but he continues to drink.
A10: Jeff drinks 6-8 beers plus shots of
liquor; reports increased tolerance to feel
“buzzed”.
A11: Get frequent hangovers, fatigue, and
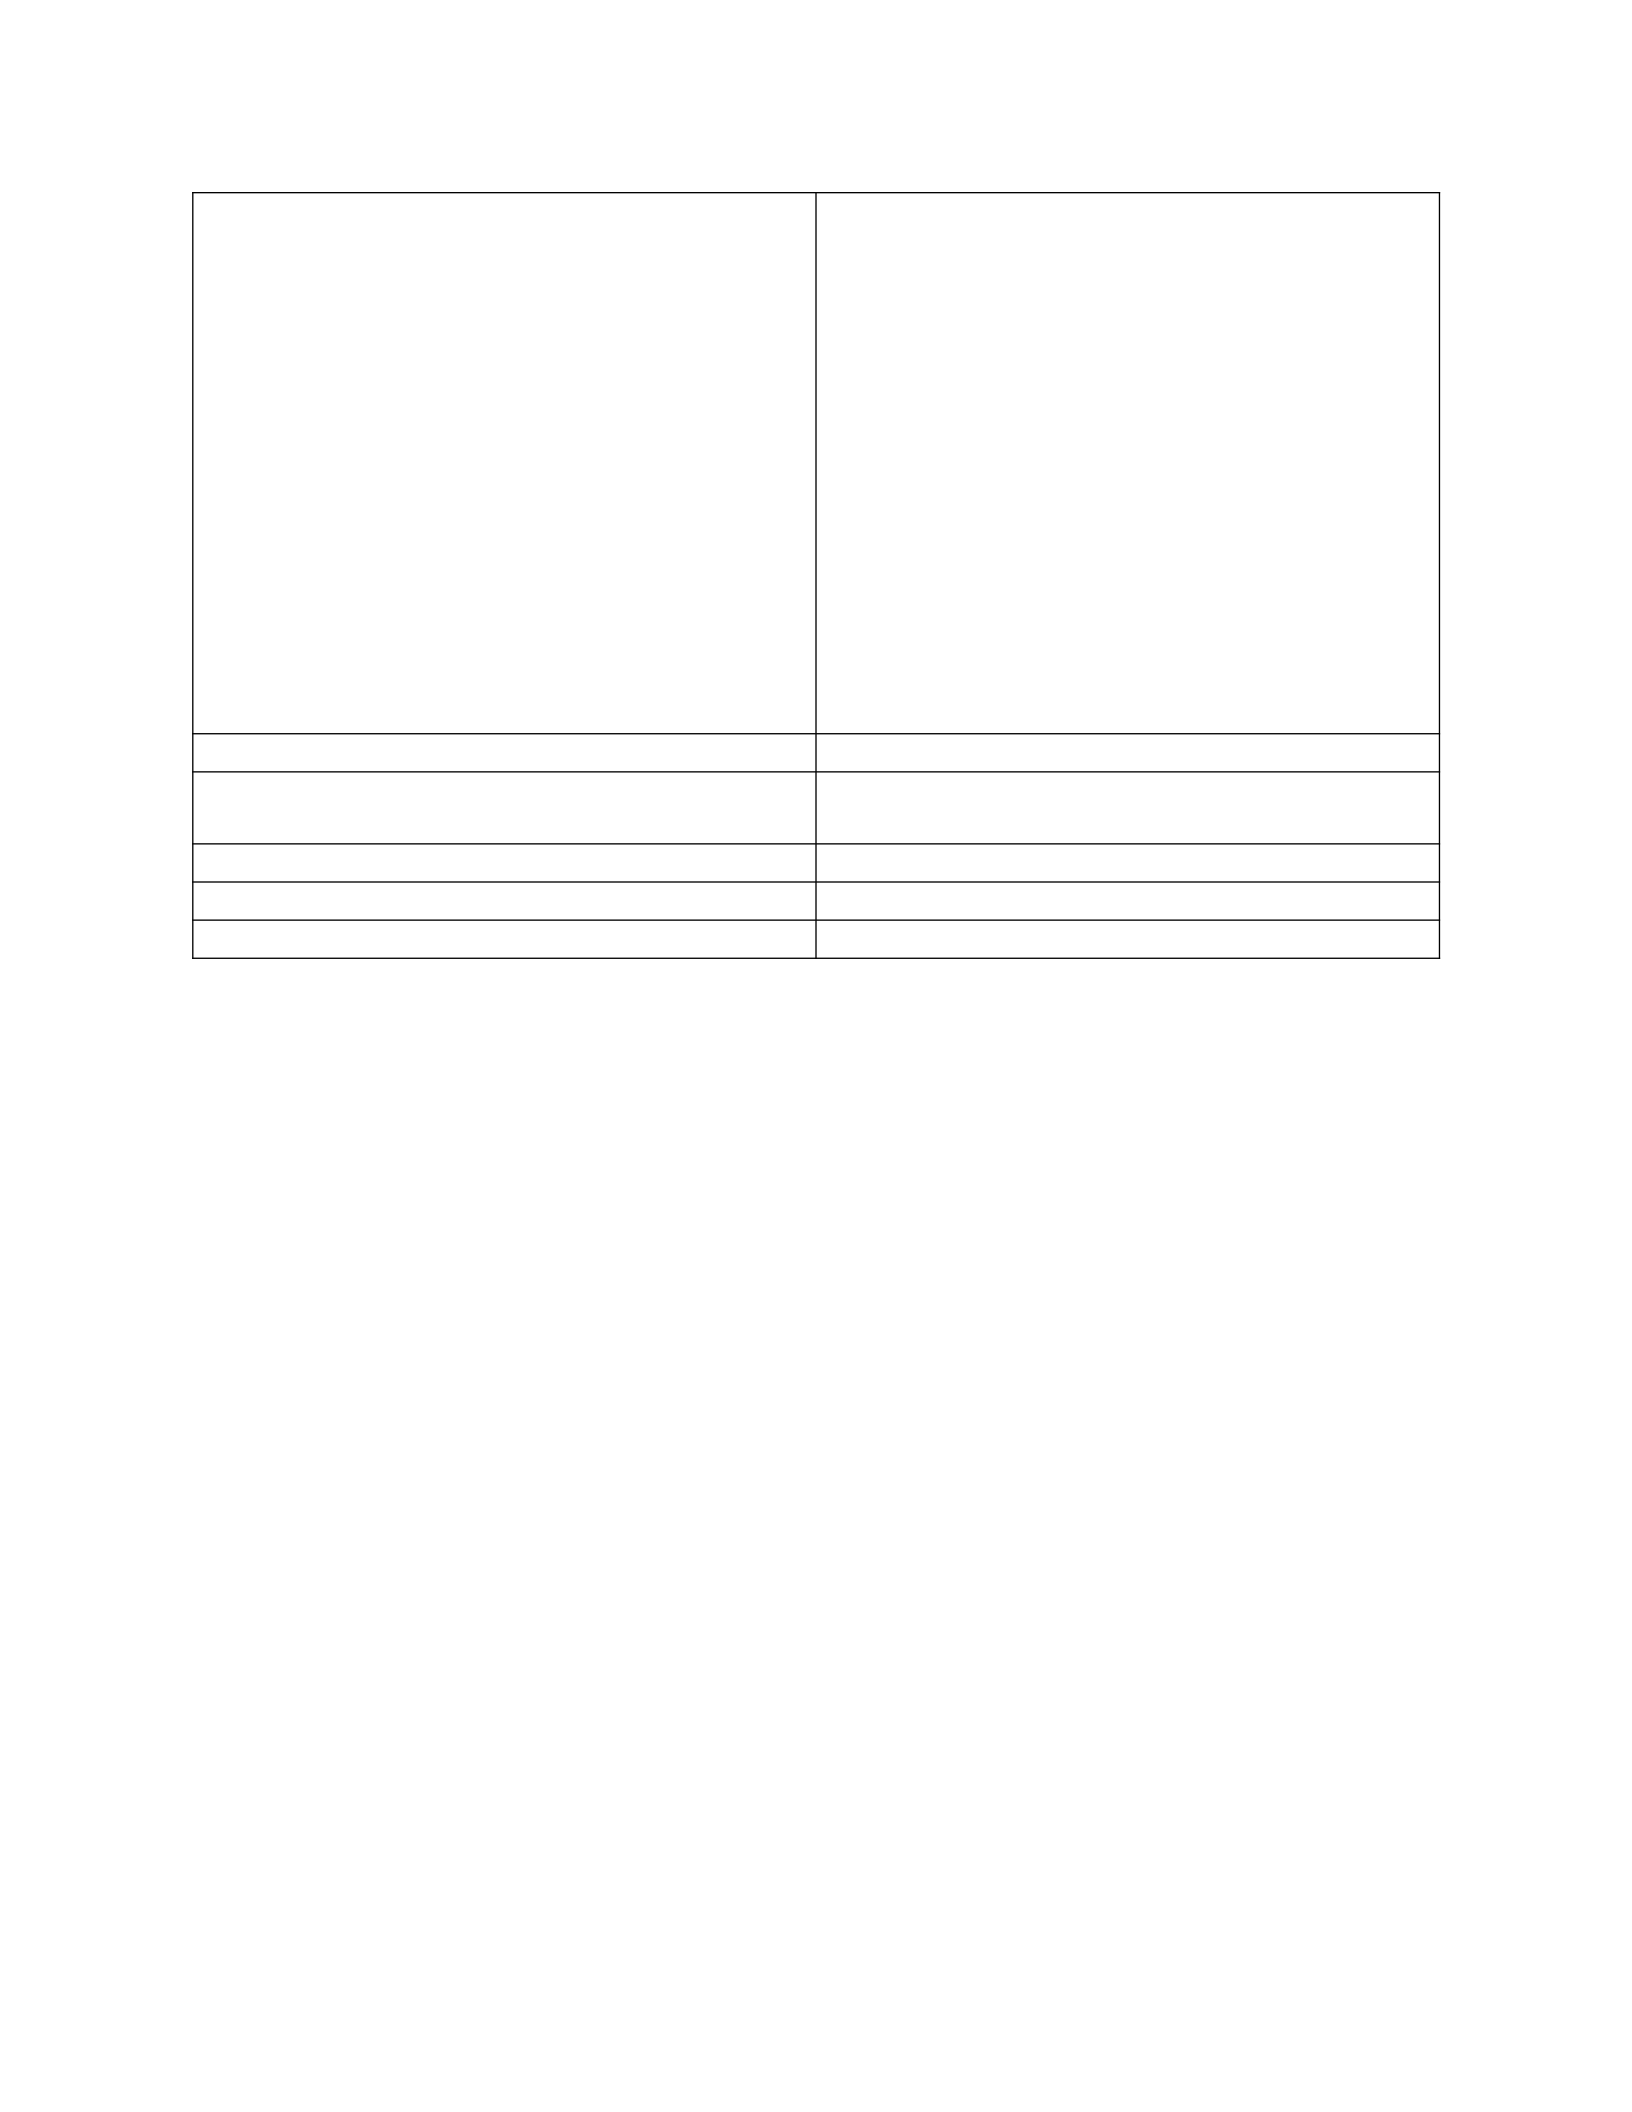
CASE STUDY: JEFF 4
physical or psychological problem that is
likely to have been caused or exacerbated by
alcohol.
10. Tolerance, as defined by either of the
following: a. A need for markedly increased
amounts of alcohol to achieve intoxication or
desired effect. b. A markedly diminished
effect with continued use of the same amount
of alcohol.
11. Withdrawal, as manifested by either of the
following: a. The characteristic withdrawal
syndrome for alcohol (refer to Criteria A and
B of the criteria set for alcohol withdrawal). b.
Alcohol (or a closely related substance, such
as a benzodiazepine) is taken to relieve or
avoid withdrawal symptoms.
preoccupation with the next drink.
Criterion B:
Criterion C:
Criterion D:
Criterion E:
Criterion F:
Other DSM-5-TR Conditions Considered
There were several severe depressive symptoms and episodes that were considered when
making a diagnosis. In the DSM-5-TR, recurrent depressive episodes can also occur in F31.4
Bipolar I Disorder, Current Episode Depressed (APA, 2022). This diagnosis was ruled out
because Jeff does not have a history of manic or hypomanic episodes. He denied any periods of
elevated mood, decreased need for sleep, or impulsive/risky behaviors which are required for a
Bipolar I diagnosis.
Developmental Theories and/or Systemic Factors
Erik Erikoson’s Psychological Theory outlines eight stages of development where
individuals must resolve specific identity conflict (e.g., intimacy vs. isolation). Successful
resolution leads to psychological strength, whereas failure can result in maladaptive behaviors or

CASE STUDY: JEFF 5
emotional distress (Lippard & Nemeroff, 2020). In Jeff’s case, unresolved conflict during the
intimacy stage may contribute to emotional dysregulation and substance dependence.
From a systemic point of view, a clinician could consider Bronfenbrenner’s Ecological Systems
Theory to review Jeff’s case. This theory emphasizes the impact of layered environmental
systems such as, family, peers, work, and society, and how it affects behavior. Jeff’s alcohol use
appears to be reinforced by his family’s normalization of drinking, previous work culture where
drinking was tolerated, and even in cultural norms surrounding masculinity and substance use.
During his interview, Jeff states that is okay for men to drink, because “that’s what men do.”
Long term exposure to dysfunctional environments that normalize unhealthy coping can lead to
developmental disruptions such as addiction, and interpersonal conflict (“Chapter 2—Influence
of Substance Misuse on Families,” 2020).
Multicultural and/or Social Justice Considerations
Jeff was raised in a family where daily alcohol consumption was a normalized,
particularly with the men. This reflects a cultural script around masculinity, that emotional
vulnerability is minimized and substance use is often an acceptable coping mechanism. These
cultural norms can hinder insight into the client’s condition and delay help-seeking behaviors.
Jeff’s resistance to treatment to mental health labeling may reflect internalized stigma. Most men
in the working class, often face barriers in acknowledging and engaging with mental services due
to societal expectations around strength and self-reliance (Himmelstein & Sanchez, 2020). As
clinicians, we must approach such cases with humility, avoid assumptions, and instead explore
how systemic messages about gender, mental health, and addiction influence behavior and
openness to change.

CASE STUDY: JEFF 6
Treatment Recommendations
Key Issues for Treatment
Jeff’s alcohol use appears to be chronic, escalating and impairing his occupational
functioning (i.e., at risk of being fired).
Jeff appears to also suffer from depression that is untreated and could be contributing to
his substance use.
Jeff has a strained relationship with his ex-wife and children. He will not stop drinking so
that he can be around his children.
Recommendations for Individual Counseling
It is recommended that Jeff participate in Motivational Interviewing treatment. This will
engage Jeff in recognizing the impact of his alcohol use, with the hope that it will enhance his
motivation to change and build autonomy in treatment planning (Miller & Rollnick, 2023). Jeff
often minimizes the impact of drinking. Motivational Interviewing is a non-confrontational
approach that has been proven to decrease resistance and increase client engagement. This
approach keeps Jeff’s value, autonomy and cultural norms surrounding masculinity at the
forefront, allowing him to explore change without feeling shame.
To address Jeff’s secondary diagnosis of Major Depressive Disorder, the clinician may
consider using Behavior Activation as another form of treatment. This approach would increase
Jeff’s engagement in activities that do not involve the consumption of alcohol but still feel
rewarding for him. This would improve his mood and break the cycle of avoidance and inactivity
associated with depression. Behavioral Activation helps the client by scheduling meaningful,
achievable activities to increase reinforcement and build daily structure. It also helps prevent
relapses by reducing the amount of idle time that is often filled with drinking (Martell, 2021).

CASE STUDY: JEFF 7
As for medication recommendations, it is recommended that Jeff be prescribed with
medication to help treat the symptoms that are consistent with the depression he is experiencing.
Although he is not currently having an episode, his symptoms appear to be recurrent. He has
reported that these symptoms have affected his day-to-day functioning in the past. Anti-
depressants may help stabilize Jeff’s mood, improve his energy, and reduce suicidal ideations,
which could aid in his engagement in therapy (Cuijpers et al., 2021). Medication would be part
of a collaborative effort along with therapy to address his condition.
Special Considerations
When a client presents with co-occurring disorders like Jeff, clinical decision making can
become complex. Sometimes the disorders interact with one, masking the symptoms of the other.
Because of this, counselors must approach each diagnosis and treatment planning systemically.
The best way to prioritize treatment planning is to assess which diagnosis is the most impairing.
The clinician will need to ensure safety and stability with the client. If one of the diagnoses is
affecting the client’s functioning and safety, that must be addressed before continuing therapy. In
Jeff’s case his symptoms intertwine between diagnosis so, both disorders can be addressed
simultaneously using integrated treatment.
Substance use can mimic, mask, or worsen other mental health symptoms. The clinician
must rule out substance-induced disorders before confirming a co-occurring condition. Often
time depression symptoms can stem from alcohol’s depressant effects or withdrawal. With Jeff,
depression redates beyond periods of substance use, confirming it as a primary mood disorder,
not substance induced.

CASE STUDY: JEFF 8
References

CASE STUDY: JEFF 9
American Psychiatric Association. (2022). Diagnostic and statistical manual of mental disorders
(5th-TR). American Psychiatric Association.
Chapter 2—Influence of Substance Misuse on Families. (2020). In www.ncbi.nlm.nih.gov.
Substance Abuse and Mental Health Services Administration (US).
https://www.ncbi.nlm.nih.gov/books/NBK571087/
Cuijpers, P., Oud, M., Karyotaki, E., Noma, H., Quero, S., Cipriani, A., Arroll, B., & Furukawa,
T. A. (2021). Psychologic Treatment of Depression Compared With Pharmacotherapy
and Combined Treatment in Primary Care: A Network Meta-Analysis. The Annals of
Family Medicine, 19(3), 262–270. https://doi.org/10.1370/afm.2676
Lippard, E., & Nemeroff, C. (2020). The Devastating Clinical Consequences of Child Abuse and
Neglect: Increased Disease Vulnerability and Poor Treatment Response in Mood
Disorders. American Journal of Psychiatry, 177(1), 20–36.
https://doi.org/10.1176/appi.ajp.2019.19010020
Martell, C. R. (2021). BEHAVIORAL ACTIVATION FOR DEPRESSION : a clinician 's guide.
Guilford.
Miller, W. R., & Rollnick, S. (2023). Motivational Interviewing: Helping People Change and
Grow (4th ed.). Guilford Press.
Saunders, J. B., Aasland, O. G., Babor, T. F., de la Fuente, J. R., & Grant, M. (1993).
Development of the Alcohol Use Disorders Identification Test (AUDIT): WHO
collaborative project on early detection of persons with harmful alcohol consumption--II.
Addiction, 88(6), 791–804. https://doi.org/10.1111/j.1360-0443.1993.tb02093.x

