



2
TREATMENT PLAN (CP-TP) ASSIGNMENT: CLAIRE STANDISH
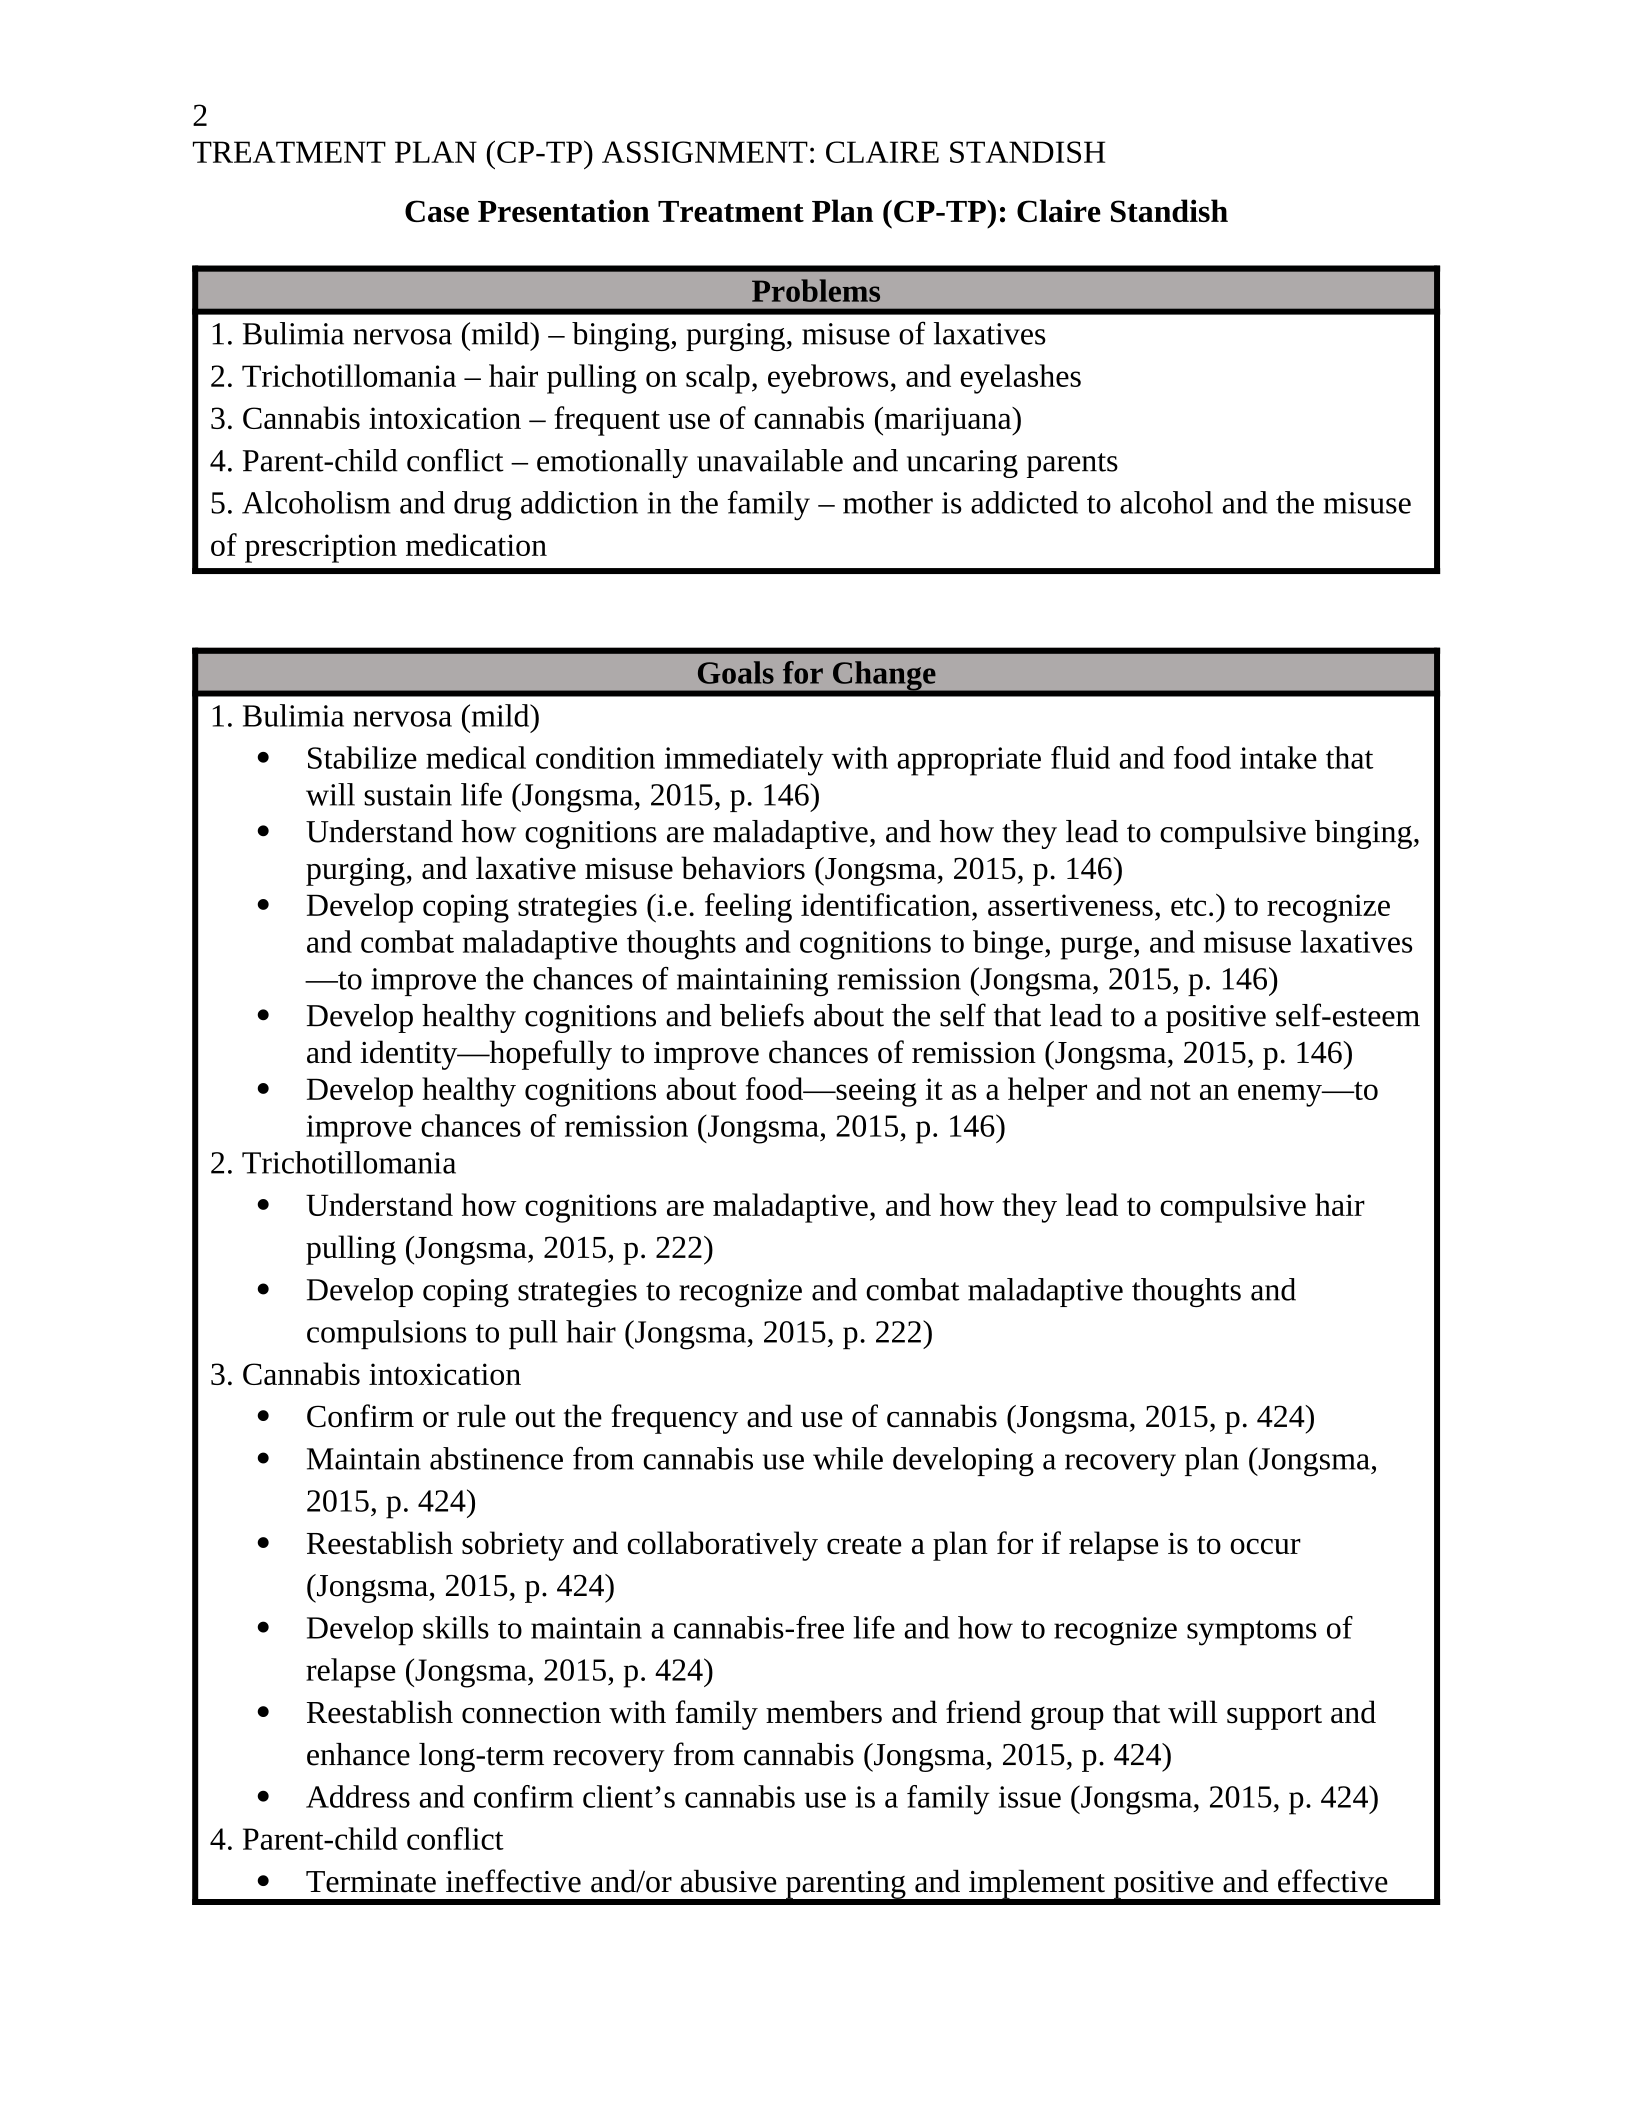
Case Presentation Treatment Plan (CP-TP): Claire Standish
Problems
1. Bulimia nervosa (mild) – binging, purging, misuse of laxatives
2. Trichotillomania – hair pulling on scalp, eyebrows, and eyelashes
3. Cannabis intoxication – frequent use of cannabis (marijuana)
4. Parent-child conflict – emotionally unavailable and uncaring parents
5. Alcoholism and drug addiction in the family – mother is addicted to alcohol and the misuse
of prescription medication
Goals for Change
1. Bulimia nervosa (mild)
Stabilize medical condition immediately with appropriate fluid and food intake that
will sustain life (Jongsma, 2015, p. 146)
Understand how cognitions are maladaptive, and how they lead to compulsive binging,
purging, and laxative misuse behaviors (Jongsma, 2015, p. 146)
Develop coping strategies (i.e. feeling identification, assertiveness, etc.) to recognize
and combat maladaptive thoughts and cognitions to binge, purge, and misuse laxatives
—to improve the chances of maintaining remission (Jongsma, 2015, p. 146)
Develop healthy cognitions and beliefs about the self that lead to a positive self-esteem
and identity—hopefully to improve chances of remission (Jongsma, 2015, p. 146)
Develop healthy cognitions about food—seeing it as a helper and not an enemy—to
improve chances of remission (Jongsma, 2015, p. 146)
2. Trichotillomania
Understand how cognitions are maladaptive, and how they lead to compulsive hair
pulling (Jongsma, 2015, p. 222)
Develop coping strategies to recognize and combat maladaptive thoughts and
compulsions to pull hair (Jongsma, 2015, p. 222)
3. Cannabis intoxication
Confirm or rule out the frequency and use of cannabis (Jongsma, 2015, p. 424)
Maintain abstinence from cannabis use while developing a recovery plan (Jongsma,
2015, p. 424)
Reestablish sobriety and collaboratively create a plan for if relapse is to occur
(Jongsma, 2015, p. 424)
Develop skills to maintain a cannabis-free life and how to recognize symptoms of
relapse (Jongsma, 2015, p. 424)
Reestablish connection with family members and friend group that will support and
enhance long-term recovery from cannabis (Jongsma, 2015, p. 424)
Address and confirm client’s cannabis use is a family issue (Jongsma, 2015, p. 424)
4. Parent-child conflict
Terminate ineffective and/or abusive parenting and implement positive and effective
3
TREATMENT PLAN (CP-TP) ASSIGNMENT: CLAIRE STANDISH
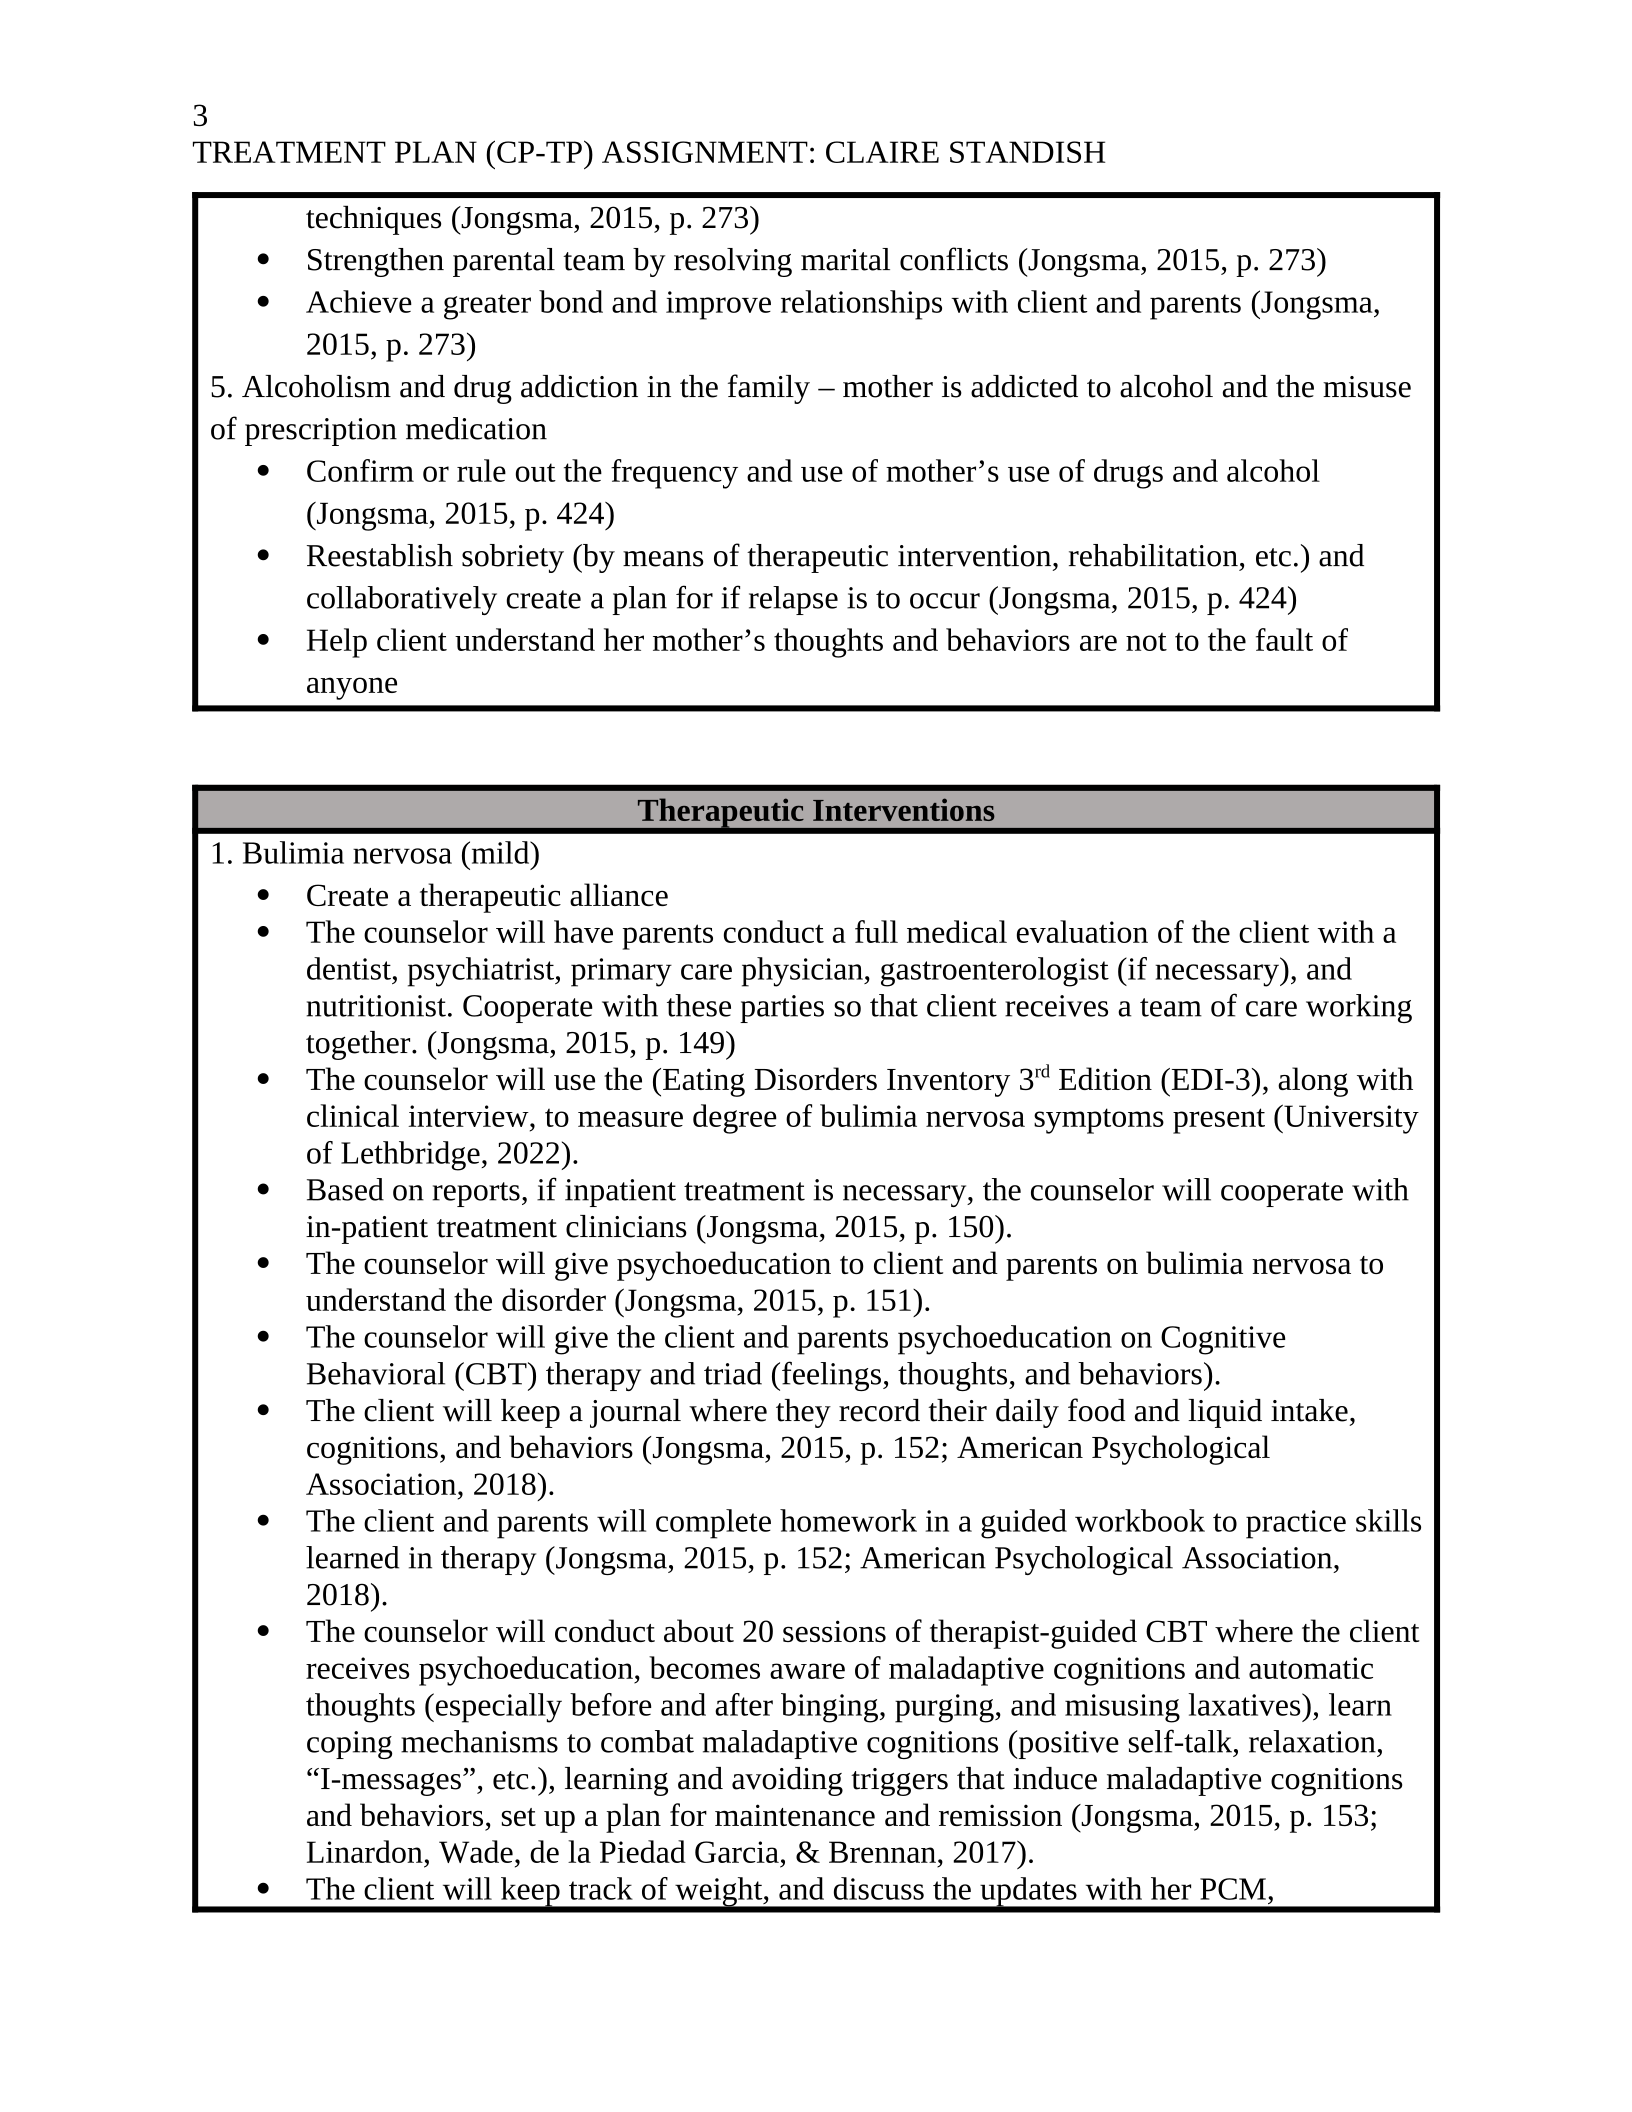
techniques (Jongsma, 2015, p. 273)
Strengthen parental team by resolving marital conflicts (Jongsma, 2015, p. 273)
Achieve a greater bond and improve relationships with client and parents (Jongsma,
2015, p. 273)
5. Alcoholism and drug addiction in the family – mother is addicted to alcohol and the misuse
of prescription medication
Confirm or rule out the frequency and use of mother’s use of drugs and alcohol
(Jongsma, 2015, p. 424)
Reestablish sobriety (by means of therapeutic intervention, rehabilitation, etc.) and
collaboratively create a plan for if relapse is to occur (Jongsma, 2015, p. 424)
Help client understand her mother’s thoughts and behaviors are not to the fault of
anyone
Therapeutic Interventions
1. Bulimia nervosa (mild)
Create a therapeutic alliance
The counselor will have parents conduct a full medical evaluation of the client with a
dentist, psychiatrist, primary care physician, gastroenterologist (if necessary), and
nutritionist. Cooperate with these parties so that client receives a team of care working
together. (Jongsma, 2015, p. 149)
The counselor will use the (Eating Disorders Inventory 3rd Edition (EDI-3), along with
clinical interview, to measure degree of bulimia nervosa symptoms present (University
of Lethbridge, 2022).
Based on reports, if inpatient treatment is necessary, the counselor will cooperate with
in-patient treatment clinicians (Jongsma, 2015, p. 150).
The counselor will give psychoeducation to client and parents on bulimia nervosa to
understand the disorder (Jongsma, 2015, p. 151).
The counselor will give the client and parents psychoeducation on Cognitive
Behavioral (CBT) therapy and triad (feelings, thoughts, and behaviors).
The client will keep a journal where they record their daily food and liquid intake,
cognitions, and behaviors (Jongsma, 2015, p. 152; American Psychological
Association, 2018).
The client and parents will complete homework in a guided workbook to practice skills
learned in therapy (Jongsma, 2015, p. 152; American Psychological Association,
2018).
The counselor will conduct about 20 sessions of therapist-guided CBT where the client
receives psychoeducation, becomes aware of maladaptive cognitions and automatic
thoughts (especially before and after binging, purging, and misusing laxatives), learn
coping mechanisms to combat maladaptive cognitions (positive self-talk, relaxation,
“I-messages”, etc.), learning and avoiding triggers that induce maladaptive cognitions
and behaviors, set up a plan for maintenance and remission (Jongsma, 2015, p. 153;
Linardon, Wade, de la Piedad Garcia, & Brennan, 2017).
The client will keep track of weight, and discuss the updates with her PCM,

4
TREATMENT PLAN (CP-TP) ASSIGNMENT: CLAIRE STANDISH
psychiatrist, and dietician.
2. Trichotillomania – hair pulling on scalp, eyebrows, and eyelashes
In the same journal as above, the client will catalog the maladaptive cognitions and
automatic thoughts that lead to, and follow, hair pulling episodes (Jongsma, 2015, p.
222)
The counselor will administer the Massachusetts General Hospital Hair Pulling Scale
(MGH-HPS), along with clinical interview, to assess the severity and frequency of
trichotillomania behaviors (Farhat, Olfson, Levine, Si, Li, Franklin, Han-Joo, Lewin,
McGuire, Rahman, Storch, Tolin, Zickgraf, & Bloch, 2020).
The counselor will provide client and parents with psychoeducation on
trichotillomania.
Counselor will lead client through Habit Reversal Therapy (HRT) (a form of CBT),
where client will learn to become self-aware of behaviors, learn how to avoid and
redirect negative stimulus that causes hair pulling behaviors, and change stimulus
responses (i.e., replacing hair pulling with deep breathing exercises, a long walk,
playing with fidget toys, etc.) (Lee, Mpavaenda, & Fineberg, 2019)
The client will see the counselor weekly to track progress of thoughts and behaviors,
as well as to continue learning skills to restructure maladaptive cognitions and
automatic thoughts.
The counselor and client will collaborate on a preventative plan to ward off relapse.
Client will learn how to interact with her mother—as she is a trigger—and use HRT
techniques to redirect hair pulling thoughts and behaviors.
3. Cannabis intoxication – frequent use of cannabis (marijuana)
The counselor will give clients and parents psychoeducation on the dangers of
cannabis use—especially in minors) (Jongsma, 2015, p. 428).
The counselor will use the Substance Abuse Subtle Screening Inventory (SASSI-3),
and clinical interview, to determine the frequency and severity of cannabis use
(University of Lethbridge, 2022).
The counselor will assess client’s motivation for treatment and use a motivational
interview approach to assist the client in evaluating her motivation for change
(Jongsma, 2015, p. 427).
The client will participate in incentive-based weekly urine screenings to determine if
she has used within the week (Jongsma, 2015, p. 429)
The client will make a list of positive and negative aspects of cannabis use (Jongsma,
2015, p. 426)
The client will decrease the level of denial by having two close peers (not in the group
that uses cannabis) and two teachers to write letters on how the client’s cannabis if
affecting them, and how they see how the use of cannabis is negatively impacting the
client’s life (Jongsma, 2015, p. 427).
Have the client discuss what personal, social, and family factors contribute to her

5
TREATMENT PLAN (CP-TP) ASSIGNMENT: CLAIRE STANDISH
cannabis use, so that triggers situations can be recognized and dealt with that will
ignite relapse (Jongsma, 2015, p. 429).
Conduct CBT with the client, so she can identify maladaptive thoughts, and teach
coping strategies for those maladaptive thoughts (Jongsma, 2015, p. 430).
4. Parent-child conflict – emotionally unavailable and uncaring parents
The counselor will meet with the parents, as a couple, to begin working on their
parenting skills.
The counselor will use compassion to assess the parent’s current parenting strategies,
and how they cope, manage, and react to their daughter’s thoughts and behaviors
(Jongsma, 2015, p. 273).
The counselor will administer psychological testing to enhance understanding of
parenting methods and parent-child relations (Jongsma, 2015, p. 273).
The counselor will assess if there is impairment in the parent’s functioning to
determine if they can appropriately care for their child, and report whatever findings
are dangerous to the proper channels (Jongsma, 2015, p. 275).
The counselor will conduct or refer parents to marital/relationship therapy to resolve
the conflicts that are preventing them from being effective parents (Jongsma, 2015, p.
276)
The counselor will educate parents on adolescent behavior, and how to respond to the
norms of this age group. This will be done via psychoeducation in session and in
recommended literature (Jongsma, 2015, p. 276-277, 279)
The parents will learn how to appropriately praise, redirect unacceptable behavior, use
of clear and direct instruction, and use of positive reinforcement (Jongsma, 2015, p.
279)
The counselor will use CBT methods to the parents, so they can instill modeling, role-
playing, feedback, and practicing their emotional reactiveness (Jongsma, 2015, p.
280).
The parents will keep a journal, with the client, that describes their daily automatic
thoughts, cognitions, and behaviors, so they too can see how maladaptive thinking
plays into their daily lives/current parenting skills.
5. Alcoholism and drug addiction in the family – mother is addicted to alcohol and the misuse
of prescription medication
The counselor will assess how frequently the mother is abusing drugs and alcohol by
use of clinical interview and psychological assessments (Jongsma, 2015, p. 273).
If the mother is actively using, the counselor will refer the mother to seek in-patient
treatment, and medical treatment (from PCM, psychiatrist, dentist, etc.), to achieve
sobriety (Jongsma, 2015, p. 274).
The counselor will refer or conduct CBT to implement and learn skills to overcome
substance abuse (Jongsma, 2015, p. 430).
The counselor will recommend the mother to join Alcoholics Anonymous (AA) or

6
TREATMENT PLAN (CP-TP) ASSIGNMENT: CLAIRE STANDISH
Narcotics Anonymous (NA)—depending on which 12-step program would be the most
beneficial to her (Jongsma, 2015, p. 425)
Outcome Measures of Change
Self-awareness to severity of cognitions and behavior, increased self-esteem, extinction of
bulimia nervosa cognitions and behaviors, extinction of trichotillomania cognitions and
behaviors, extinction of cannabis use, improved parent-child relationship, improved parenting
skills in client’s parents, and extinction of drug and alcohol abuse in client’s mother.
Pre-post measures of bulimia nervosa, trichotillomania, and cannabis use
psychological measures (Eating Disorders Inventory 3rd Edition (EDI-3), Substance
Abuse Subtle Screening Inventory (SASSI-3), and the Massachusetts General Hospital
Hair Pulling Scale (MGH-HPS) (University of Lethbridge, 2022; Farhat, et al., 2020)
Counselor will observe change in client and parent thoughts, behaviors, and mood.
Client reports reduction and/or extinction of maladaptive cognitions and behaviors.
Client reports reduction in family conflict and disinterest
Clear reports of improved functioning in outside settings (school, home,
extracurricular activities)
A reduction of symptoms and physiological effects as noted by client’s other clinicians
involved in her care
References
American Psychological Association. (2018, March 8). Cognitive behavioral therapy for bulimia
nervosa | society of clinical psychology. Society of clinical psychology: division 12 of the

7
TREATMENT PLAN (CP-TP) ASSIGNMENT: CLAIRE STANDISH
american psychological association. https://div12.org/treatment/cognitive-behavioral-
therapy-for-bulimia-nervosa/
Farhat, L. C., Olfson, E., Levine, J. L. S., Li, F., Franklin, M. E., Han-Joo, L., Lewin, A. B.,
McGuire, J. F., Rahman, O., Storch, E. A., Tolin, D. F., Zickgraf, H. F., & Bloch, M. H.
(2020). Measuring treatment response in pediatric trichotillomania: a meta-analysis of
clinical trials. Journal of Child and Adolescent Psychopharmacology, 30(5), 306-315.
https://doi.org/10.1089/cap.2019.0103
Jongsma, A. E., Jr. (2015). The adolescent psychotherapy treatment planner (practiceplanners)
(5th ed.). Wiley.
Lee, M. T., Mpavaenda, D. N., & Fineberg, N. A. (2019). Habit Reversal Therapy in Obsessive
Compulsive Related Disorders: A Systematic Review of the Evidence and CONSORT
Evaluation of Randomized Controlled Trials. Frontiers in behavioral neuroscience, 13,
79. https://doi.org/10.3389/fnbeh.2019.00079
Linardon, J., Wade, T. D., de la Piedad Garcia, X., & Brennan, L. (2017). The efficacy of
cognitive-behavioral therapy for eating disorders: A systematic review and meta-analysis.
Journal of Consulting and Clinical Psychology, 85(11), 1080–1094.
https://doi.org/10.1037/ccp0000245.supp (Supplemental)
University of Lethbridge. (2022). Assessment instruments (counselling program). Retrieved June
20, 2022, from https://www.ulethbridge.ca/education/currlab/assesslibrary
Powered by TCPDF (www.tcpdf.org)

